Review

The Role of Clomiphene Citrate in Gonadotropin Stimulation Protocols in Poor Responders: A Mini-Review of Recent Clinical Evidence


by
Maria Papadopoulou
1,*,
Miltiadis Badagionis
2,
Fotios Vlahos
3,
Nikolaos Vlahos
2,
Alexandros Lazaridis
2,
George Mastorakos
2 and
Olga Triantafyllidou
2
1
Health Center of Northern Section of Patras, 6th Health Region (DYPE) of Peloponnese, 262 23 Patras, Greece
2
B’ Department of Obstetrics and Gynecology, Aretaieion Hospital, 115 28 Athens, Greece
3
University of Milano-Bicocca, 20126 Milan, Italy
*
Author to whom correspondence should be addressed.
Reprod. Med. 2026, 7(3), 44; https://doi.org/10.3390/reprodmed7030044
Submission received: 22 July 2026 / Revised: 22 August 2026 / Accepted: 28 August 2026 / Published: 2 September 2026
(This article belongs to the Collection Reproductive Medicine in Europe)

Abstract

Diminished ovarian reserve (DOR) and poor ovarian response (POR) remain among the most challenging conditions in assisted reproductive technology, and no optimal stimulation strategy has been established. Clomiphene citrate (CC), a selective estrogen receptor modulator that augments endogenous gonadotropin secretion and modulates the intraovarian androgenic milieu, has been proposed as an adjuvant to reduce exogenous gonadotropin requirements. This mini-review summarizes clinical evidence published between January 2015 and March 2025 on the co-administration of CC with gonadotropins in women with DOR or POR undergoing IVF/ICSI. Eleven primary studies (four randomized controlled trials, six observational cohort studies and one before–after study) were identified through a structured, PRISMA-informed literature search. Across mild, standard, and high-dose regimens, CC co-administration consistently reduced total gonadotropin consumption and stimulation duration, whereas oocyte yield, clinical pregnancy, and live-birth rates were largely comparable to conventional protocols. Cost analyses suggest a meaningful reduction in the expenditure per treatment cycle, although the cost per delivery is driven predominantly by the low absolute success rates in this population. Careful monitoring of endometrial thickness is warranted given the anti-estrogenic effect of CC, and a freeze-all strategy may be preferable when endometrial development is suboptimal. In the wider context of adjuvant therapy for POR, CC occupies a position comparable to that of letrozole: it reduces treatment burden without demonstrable improvement in live birth. Larger, adequately powered multicentre randomized trials with live birth as the primary endpoint are needed to define the role of CC in this population.

1. Introduction

Infertility is a common condition with substantial personal, social and economic consequences. According to estimates published by the World Health Organization in 2023, the lifetime prevalence of infertility is approximately 17.5%, corresponding to roughly one in six adults worldwide, with limited variation between high-income and low- and middle-income settings [1]. Within the infertile population, diminished ovarian reserve (DOR) and poor ovarian response (POR) are among the most challenging conditions in assisted reproductive technology (ART). Poor ovarian response has been reported to occur in 9–24% of ovarian stimulation cycles and affects the chance for conception significantly, with high rates of cycle cancellation and reduced chance for pregnancy [2,3,4]. Poor ovarian response to stimulation has for many years hampered progress in its management, mainly because of the lack of an agreed definition of the condition and the consequent variability in diagnosis among studies. In a systematic review of 47 randomized trials, Polyzos and Devroey identified 41 different definitions of “poor responders,” underscoring the extent of this heterogeneity [2].
The introduction of the European Society of Human Reproduction and Embryology (ESHRE)-supported Bologna criteria in 2011 provided a uniform basis for the diagnosis of POR. According to these criteria, poor response is diagnosed when at least two of the following three criteria are present: advanced maternal age (≥40 years) or any other risk factor for POR; a previous poor ovarian response (≤3 oocytes with a conventional stimulation protocol); and an abnormal ovarian reserve test (antral follicle count <5–7 or anti-Müllerian hormone <0.5–1.1 ng/mL) [5]. However, although the Bologna criteria improved research consistency, their contribution to individualized clinical decision-making has been limited, principally because they aggregate biologically distinct patients—for example a young woman with severely reduced reserve and an older woman with an age-related decline—into a single prognostic category [6].
Several years later, the Patient-Oriented Strategies Encompassing Individualized Oocyte Number (POSEIDON) criteria introduced a clinically relevant classification system for PORs, distributing them into four groups according to age, ovarian reserve biomarkers (AMH and AFC), and previous ovarian response to stimulation [7,8]. Groups 1 and 2 comprise women with adequate pre-stimulation ovarian reserve markers who nevertheless demonstrate an unexpected poor or suboptimal response, stratified by age below or above 35 years; groups 3 and 4 comprise women with expected poor response on the basis of reduced ovarian reserve markers (AFC < 5, AMH < 1.2 ng/mL), again stratified by age [7,8]. This framework replaces the binary poor-responder label with a patient-oriented concept of “low prognosis,” in which the therapeutic objective is defined as obtaining the number of oocytes required to achieve at least one euploid blastocyst for that specific woman. Standardized reporting of studies employing this classification has subsequently been proposed in the POSORT guidelines [9].
Accurate pre-treatment assessment of ovarian reserve underpins both classification systems. Anti-Müllerian hormone (AMH) and antral follicle count (AFC) are currently regarded as the most reliable biomarkers for predicting the quantitative ovarian response to stimulation, and both substantially outperform chronological age and basal follicle-stimulating hormone (FSH) [10,11,12]. In a meta-analysis of 42 studies, AMH and AFC demonstrated comparable overall discriminative performance for the prediction of poor response, with no significant difference between their summary receiver-operating-characteristic curves, although the choice of cut-off value was a major source of heterogeneity [11]. AMH has the practical advantages of relative stability across the menstrual cycle and independence from operator-dependent ultrasound assessment [13]. It should nevertheless be emphasized that these markers predict oocyte quantity rather than oocyte quality, and consequently their capacity to predict live birth in the individual patient is limited [10,13].
The clinical relevance of oocyte yield is supported by the well-documented association between the number of oocytes retrieved and the probability of live birth. In an analysis of more than 400,000 IVF cycles, Sunkara et al. demonstrated a positive relationship between oocyte number and live-birth rate up to approximately 15 oocytes, with a plateau thereafter [14]. This observation provides the biological rationale for attempting to maximize the oocyte cohort in women with DOR. A common clinical strategy has therefore been to use high doses of gonadotropins in order to recruit a greater number of follicles in such patients; however, multiple studies and meta-analyses have shown only limited benefit and a substantial increase in cost in this subgroup [15,16]. This apparent paradox reflects the fact that the recruitable follicular cohort in women with DOR is finite: once all available FSH-sensitive follicles have been recruited, further escalation of the gonadotropin dose cannot generate additional follicles and serves only to increase expenditure and patient burden.
The selective estrogen receptor modulator clomiphene citrate (CC) acts primarily by occupying hypothalamic estrogen receptors, leading to increased endogenous gonadotropin-releasing hormone (GnRH) pulse frequency and resulting in increased pituitary FSH and luteinizing hormone (LH) secretion [17]. This mechanism of action forms the basis for co-administration of CC with exogenous gonadotropins. The endogenous gonadotropins promote follicular recruitment and cohort synchronization during treatment, thereby lowering the total dose of exogenous injectable medications needed for ovulation induction [18,19].
A further biological advantage of CC in poor responders is that it modulates the androgenic milieu, which is thought to enhance the gonadotropin-supported growth of follicles [20,21]. The rise in LH induced by CC administration increases the intraovarian production of androgens, which in primate models have been shown to prime early follicular growth [20]. Moreover, androgens may act synergistically with FSH by promoting the expression of FSH receptors on granulosa cells, thereby favoring follicular growth in poor responders [21].
Previous systematic reviews and meta-analyses have reported heterogeneous and sometimes conflicting findings regarding the efficacy of CC-containing protocols in poor responders. Bechtejew et al. performed a meta-analysis of 22 studies on CC, including only RCTs, and showed that in women with expected poor ovarian response the live-birth (RR 0.9, 95% CI 0.6–1.2) and clinical pregnancy rates (RR 1.0, 95% CI 0.8–1.4) were similar, but the amount of FSH required for stimulation was significantly decreased [18]. Recent studies involving only POSEIDON-defined DOR populations reported neutral reproductive outcomes with reduced medication use [19,22]. The most recent ESHRE guideline on ovarian stimulation, updated in 2025, devotes specific attention to pre-treatment and adjuvant strategies in low responders, reflecting the persistent clinical uncertainty in this area [23]. Thus, the role of CC in ovarian stimulation for women with DOR remains unclear. This mini-review aims to summarize recent available evidence on the use of CC in combination with gonadotropins for women with DOR and POR and to clarify its place in current IVF practice.

2. Pharmacology and Mechanism of Action of Clomiphene Citrate

A clear understanding of the pharmacological properties of CC is helpful in interpreting the heterogeneous clinical findings reported in poor responders, since several of the drug’s advantages and disadvantages in this population derive directly from its molecular behaviour.
Clomiphene citrate is not a single compound but a racemic mixture of two geometric isomers, the cis-isomer zuclomiphene and the trans-isomer enclomiphene, with the cis-isomer constituting approximately 30–50% of commercial preparations [24]. The two isomers exhibit mixed estrogenic and antiestrogenic properties: available data indicate that zuclomiphene possesses greater estrogenic activity, whereas enclomiphene is principally responsible for the antiestrogenic effect that drives gonadotropin release [24]. The isomers also differ substantially in their pharmacokinetics. Single-dose studies in healthy volunteers have shown that zuclomiphene has a considerably longer half-life than enclomiphene, with detectable concentrations persisting for longer than one month after administration, a finding attributed to stereo-specific enterohepatic recycling or tissue sequestration [24]. This prolonged persistence of the estrogenic isomer is clinically relevant because it implies that pharmacological activity may extend beyond the conventional five-day treatment window and, in repeated cycles, may accumulate.
Clomiphene citrate interacts with estrogen-receptor-containing tissues throughout the reproductive tract, including the hypothalamus, pituitary, ovary, endometrium, vagina and cervix. It competes with endogenous estrogen for receptor-binding sites and may delay the replenishment of intracellular estrogen receptors [24]. At the hypothalamic level, this receptor blockade interrupts the negative feedback exerted by circulating estradiol, increasing the frequency of GnRH pulses and consequently augmenting pituitary secretion of FSH and LH [17]. In the context of controlled ovarian stimulation, this endogenous gonadotropin drive acts in addition to the administered exogenous gonadotropins, which constitutes the pharmacological basis of the dose-sparing effect observed consistently across clinical studies [18,19].
A second, ovarian mechanism may be of particular relevance in women with reduced ovarian reserve. The CC-induced rise in LH stimulates theca-cell androgen production, and intraovarian androgens have been shown in primate models to promote the initiation and early growth of follicles [20]. Androgens additionally upregulate granulosa-cell FSH-receptor expression and stimulate the intraovarian insulin-like growth factor-I system, thereby amplifying the response of the follicle to FSH [21,25]. This androgen-mediated sensitization provides a plausible explanation both for the gonadotropin-sparing effect and for the improvements in laboratory parameters reported in some studies of CC co-treatment.
The same receptor-level mechanism, however, accounts for the principal drawback of CC. Because the drug does not act selectively on the hypothalamus, its antiestrogenic activity extends to peripheral estrogen-responsive tissues, most importantly the endometrium and the endocervix [24]. Depletion of endometrial estrogen receptors during the proliferative phase may impair endometrial growth and receptivity, an effect that is clinically apparent as reduced endometrial thickness. This constitutes the main mechanistic distinction between CC and the aromatase inhibitor letrozole: letrozole reduces estradiol synthesis without occupying or depleting estrogen receptors, so that once the drug is cleared, the endometrium is exposed to rising estradiol concentrations without residual receptor blockade [19]. This difference is of limited consequence in a segmented (freeze-all) strategy but may be decisive when a fresh embryo transfer is planned.

3. Materials and Methods

We performed a structured electronic literature search of the PubMed/MEDLINE, Google Scholar, and Scopus databases, following the main principles of the PRISMA 2020 statement for study identification, screening, and inclusion [26,27,28]. The searched articles examined the efficacy of CC plus gonadotropins in IVF/ICSI protocols in women with DOR and/or POR. The Boolean search strategy using free-text keywords was: clomiphene, clomiphene citrate, gonadotropin, FSH, hMG, menotropin, ovarian stimulation, controlled ovarian stimulation, COS, IVF, ICSI, in vitro fertilization, assisted reproduction, assisted reproductive technology. The search was limited to human research published in the English language from January 2015 to March 2025. The terms were combined as (clomiphene OR “clomiphene citrate”) AND (gonadotropin OR gonadotrophin OR FSH OR hMG OR menotropin) AND (“ovarian stimulation” OR “controlled ovarian stimulation” OR COS OR IVF OR ICSI OR “in vitro fertilization” OR “assisted reproduction” OR “assisted reproductive technology”), and the same string, using free-text terms without controlled vocabulary, was applied to all three databases. Population-restricting terms such as “poor responder”, “poor ovarian response”, “diminished ovarian reserve”, “low prognosis”, “POSEIDON” and “Bologna” were deliberately omitted from the retrieval string. This was a considered decision intended to maximize sensitivity: a substantial proportion of trials of CC co-treatment do not carry these descriptors in the title or abstract, and several of the studies ultimately included define their populations only by centre-specific criteria, so that a population-filtered search would have retrieved fewer eligible records. Population eligibility was applied instead at the screening stage, as reflected below in the exclusion of 28 records at title and abstract for not concerning poor-responder or diminished-reserve populations.
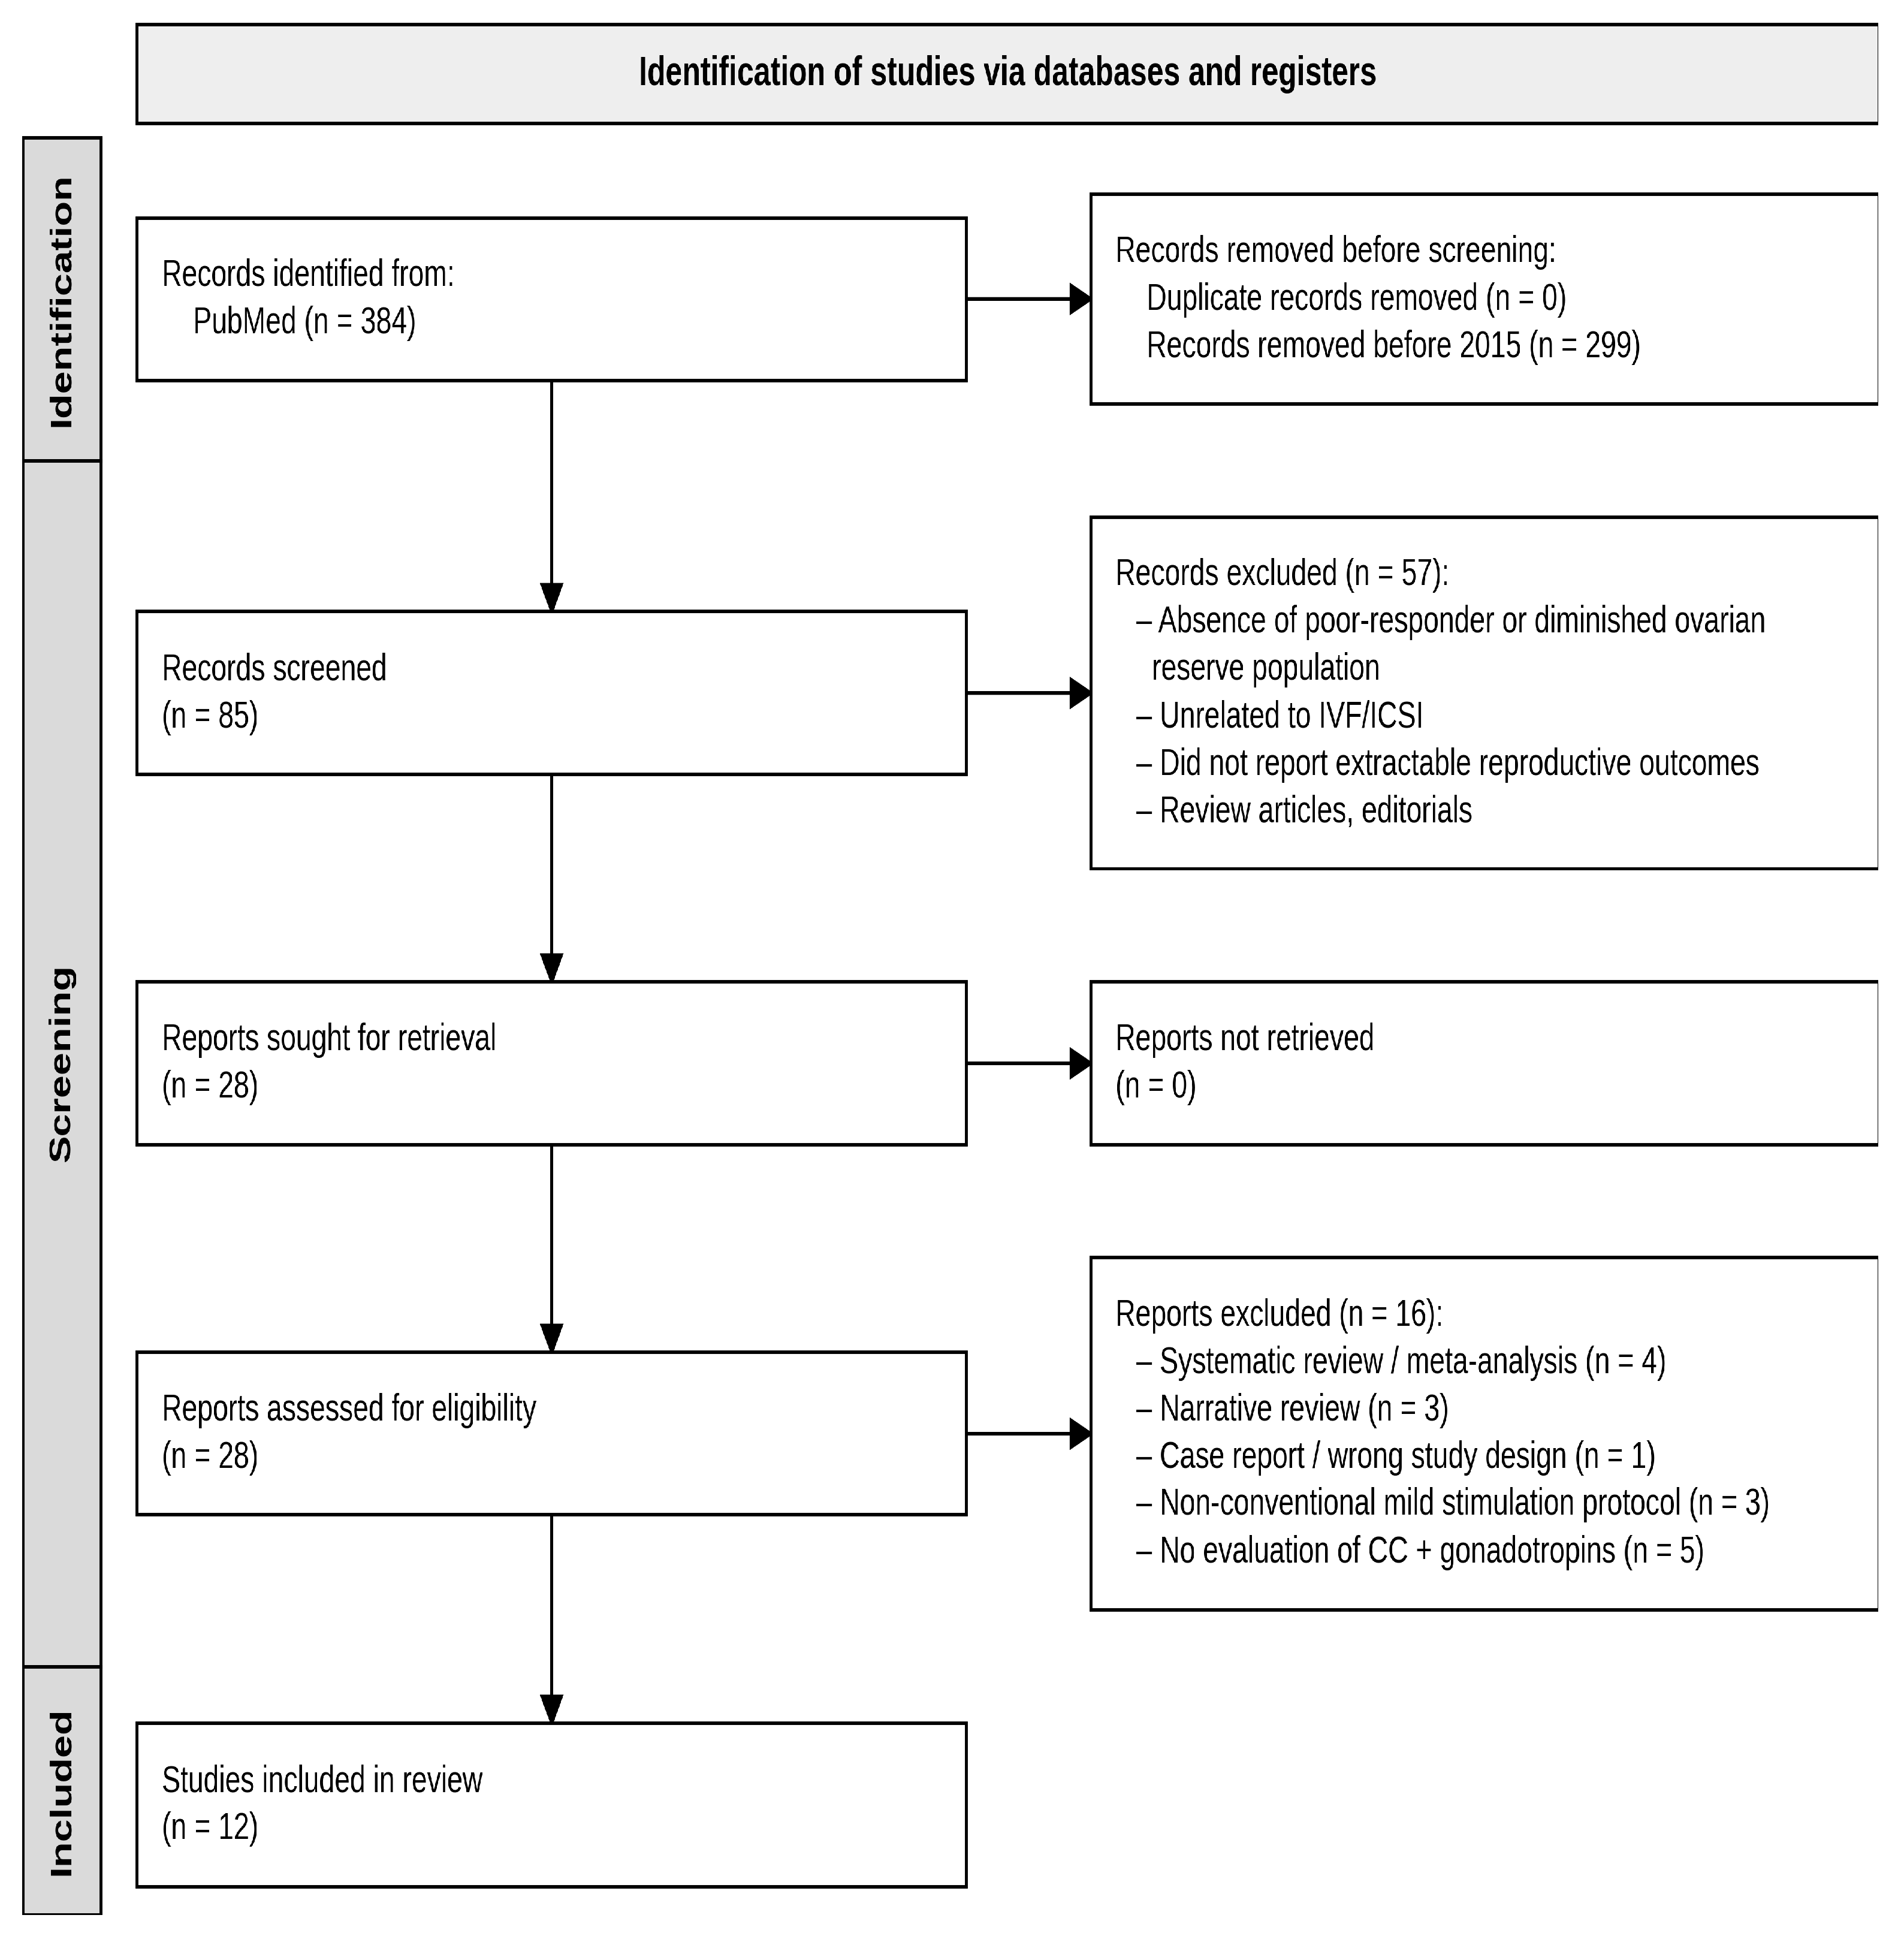
All 384 identified records were screened for relevance in two stages. First, all citations published prior to 2015 were excluded (n = 299). The titles and abstracts of the remaining 85 citations were screened by two authors. In total, 57 of these records were excluded because they did not include poor-responder or diminished-reserve populations (28), were unrelated to IVF/ICSI (8), were reviews (10), meta-analyses (5), editorials (1), or case reports (5). Second, 28 full-text articles that met the inclusion criteria were read in full. Of these, 16 were excluded for the following reasons: no extractable reproductive outcomes reported (7), inappropriate study design (1), non-conventional mild stimulation protocol (3), and no evaluation of CC plus gonadotropins (5).
We included only studies enrolling women with POR according to the Bologna criteria, the POSEIDON criteria, or other centre-specific criteria, using CC in combination with low, standard, or high doses of gonadotrophins and reporting at least one IVF or ICSI outcome, such as the number of oocytes, mature oocytes, embryo development, clinical pregnancy, and/or live-birth rates. The quality of the evidence was assessed using the five GRADE domains: risk of bias (within studies), inconsistency (between studies), indirectness (of evidence), publication bias (the possibility of research publication being influenced by the outcome), and overall certainty. Two authors performed a descriptive assessment of study quality for the different domains based on study design, assessment of important confounders, participant inclusion and exclusion criteria, outcome data availability, and reporting of outcomes. The selection process is shown in the PRISMA flow diagram (Figure 1).
Because the diagnostic criteria applied across the included studies differed substantially, the two principal classification systems encountered are summarized in Table 1 to facilitate interpretation of the pooled evidence.

4. Results

The review includes eleven primary studies on CC in combination with gonadotropins for the treatment of women with DOR. These comprise four randomized controlled trials (RCTs) [29,30,31,32], six observational cohort studies [33,34,35,36,37,38] and one before–after study conducted in the same patients [39]. In addition, one narrative review with an updated meta-analysis [40] was consulted as a source of secondary evidence rather than as a primary study; it is discussed in Section 5 and is not tabulated, so that the twelve records retained after full-text assessment (Figure 1) comprise these eleven primary studies together with that secondary source. The characteristics and main outcomes of the eleven primary studies are summarized in Table 2. For clarity of the evidence hierarchy, the sources drawn upon in this review are of four kinds and are treated distinctly throughout: randomized controlled trials [29,30,31,32]; non-randomized comparative studies [33,34,35,36,37,38,39]; systematic reviews and meta-analyses, discussed as secondary evidence in Section 5.2 [15,16,18,22,41]; and narrative reviews and clinical guidelines, cited for context only [23,40].

4.1. Stimulation Protocols Evaluated

GnRH antagonist-based protocols were the most common, using either standard or flexible antagonist regimens [29,30,31,32,35,36,38]. Two studies used microdose GnRH agonist flare protocols [31,36]. Progestin-primed ovarian stimulation (PPOS) was evaluated in one retrospective cohort study [34]. “Long CC” protocols, in which women receive CC throughout the entire stimulation period in order to reduce doses of gonadotropins and prevent premature ovulation by blocking the positive feedback loop through its anti-estrogenic effect, have also been reported [33]. The effect of CC priming prior to the initiation of gonadotropin stimulation was also evaluated in a separate retrospective cohort study [35]. Gonadotropin doses varied widely among studies, ranging from 75–150 IU/day to 300–450 IU/day, allowing the effect of CC to be evaluated across the full range of stimulation intensity.

4.2. Gonadotropin Consumption and Stimulation Duration

In almost all protocols, the addition of CC was strongly associated with reduced gonadotropin consumption. This effect was observed across the full range of stimulation doses: in mild or low-dose regimens [30,37,39,40], in high-dose strategies [36,38], and in PPOS cycles [34]. Liu et al. reported that adding 50 mg/day CC to a PPOS protocol reduced the total human menopausal gonadotropin (hMG) dose (2998.63 ± 1051.09 vs. 3399.18 ± 820.75 IU, p < 0.001) and stimulation duration (10.21 ± 3.56 vs. 11.27 ± 2.56 days, p < 0.001) [34]. In the randomized trial by Pilehvari et al., a minimal-stimulation regimen combining CC 100 mg/day with hMG 150 IU/day required substantially less gonadotropin than a conventional antagonist protocol using at least 300 IU/day (1046 ± 596 vs. 2806 ± 583 IU) [30]. More recently, Mandelbaum et al. showed that a “long CC” protocol, in which ongoing CC stimulation was used throughout the cycle of a GnRH antagonist stimulation protocol, achieved comparable mature oocyte yields to the standard 5-day CC regimen plus antagonist protocol (median 5 vs. 4.5, p = 0.922) but significantly reduced the total dose of gonadotropins and the incidence of premature ovulation (0.3% vs. 3.0%, p = 0.019) [33]. Similar outcomes—decreased total dose of gonadotropins, shortened stimulation periods, and increased follicle-to-oocyte ratios—were achieved with the CC-priming protocol described by Liu et al. when compared with a conventional antagonist protocol [35].

4.3. Reproductive Outcomes

In contrast, the impact of CC on the main reproductive endpoints was largely neutral. Most studies reported a comparable number of oocytes and embryos in CC and non-CC regimens [30,33,34,36,37]. However, Siristatidis et al. reported a significantly lower oocyte yield with a mild CC-based protocol compared with conventional stimulation (median 1 vs. 3, p < 0.001) in 58 Bologna-defined poor responders. Nevertheless, the clinical pregnancy rate (12.1% vs. 20%, p = 0.412) and live-birth rate (9.1% vs. 12%, p = 0.719) were similar between the two groups [29]. Similarly, in PPOS cycles the addition of CC was not associated with significant differences in clinical pregnancy rate (OR 1.286, 95% CI 0.671–2.470, p = 0.441) or live-birth rate (OR 1.390, 95% CI 0.478–3.990) after adjustment for confounders [34].
Only one randomized trial reported superior outcomes with a non-CC strategy. Schimberni et al. found higher clinical pregnancy rates with the short GnRH agonist protocol than with the CC-based and GnRH antagonist protocols (29.3% vs. 5.9% vs. 14.1%, p = 0.028). The implantation rate was significantly lower in the CC group (4.8%) than in both the GnRH antagonist (9.3%, p = 0.040) and the short GnRH agonist groups (19.2%, p = 0.003) [31].
Four studies suggested some benefit of CC co-administration, mainly in laboratory parameters. Moffat et al. conducted a double-blinded, placebo-controlled RCT including 114 Bologna-defined poor responders divided into four groups. Patients who received CC 100 mg (days 3–7) in combination with low-dose gonadotropins (150 IU/day) had a significantly higher number of blastocysts than all other protocols (1.77 vs. 0.83, p = 0.006), despite a similar oocyte yield. The overall live-birth rate across all groups was 12.3% [32]. Liu et al. found a higher follicle-to-oocyte index following CC priming; however, the cumulative ongoing pregnancy rates did not differ (adjusted OR 0.761, 95% CI 0.300–1.933, p = 0.566) [35]. Triantafyllidou et al. found that adding CC to high-dose hMG (300 IU/day) resulted in higher estradiol, more follicles, more oocytes, more embryos, and lower cancellation rates, but without improvement in clinical pregnancy or live-birth rates [38]. Ochin et al. reported a higher oocyte yield and improved cumulative pregnancy rates with a combination of CC plus low-dose rFSH (75–112.5 IU/day) compared with a long GnRH agonist protocol (≥150 IU/day). However, this was a before–after observational study in the same patients (n = 65), which limits the strength of these conclusions [39].

5. Discussion

In this mini-review, we evaluated 12 studies that investigated the use of CC in combination with gonadotropins for the treatment of women with DOR or POR undergoing IVF/ICSI over the last decade. The main finding was that the addition of CC reduced gonadotropin doses and sometimes improved stimulation characteristics but did not translate into improved reproductive outcomes, including clinical pregnancy and live-birth rates.

5.1. The Gonadotropin-Sparing Advantage

From a pharmacoeconomic perspective, the main advantage of CC co-administration is reduced gonadotropin consumption. This has been demonstrated by several studies and meta-analyses, including large randomized and comparative studies. In the meta-analysis by Bechtejew et al., which pooled a large number of randomized and comparative studies comprising more than 1000 treatment cycles in which CC was co-administered with gonadotropins, the total amount of FSH required for ovarian stimulation was significantly reduced [18]. Youssef et al. also estimated the reduction in the required dose per cycle, which averaged 1700 to 2000 IU across all studies (WMD = −2027; 95% CI −2583 to −1470; p < 0.00001), with a significant reduction in the duration of stimulation as well (WMD −1.79 days, 95% CI −2.75 to −0.84) [16]. The same result was observed in other studies [30,34,35]. The combination of low-dose gonadotropins with CC reduces gonadotropin expenditure per initiated cycle and may reduce treatment burden, which is of particular relevance in less affluent settings where the cost of medication is a major concern. Its cost-effectiveness per live birth, however, remains uncertain, and the approach does not change live-birth rates.

5.2. Clinical Outcome Neutrality

Most studies showed neutral effects on the major clinical outcomes. Oocyte yield, embryo numbers, clinical pregnancy rates, and live-birth rates were similar across the various stimulation protocols using CC compared with their respective controls [29,30,33,34,36,37]. Three meta-analyses confirmed these neutral effects. Bechtejew et al. reported no significant difference in clinical pregnancy (RR 1.0, 95% CI 0.8–1.4) or live-birth rates (RR 0.9, 95% CI 0.6–1.2) in poor responders [18]. Youssef et al. found no difference in ongoing pregnancy rates between women treated with gonadotropins combined with oral compounds and those treated with high-dose gonadotropins alone (RR 0.90, 95% CI 0.63–1.27) [16]. Zhang et al., in a network meta-analysis of adjuvant stimulation protocols in POR, ranked CC the lowest of the 10 interventions for clinical pregnancy (SUCRA 14.1%) and reported neutral effects of CC co-administration on reproductive outcomes (OR 0.60, 95% CI 0.17–2.15) despite lower medication use (WMD −1760 IU, 95% CI −2890.55 to −629.45) [15]. This evidence is further supported by a Cochrane analysis, which showed that live-birth rates with CC–gonadotropin stimulation protocols were similar to those achieved with conventional stimulation in poor responders [41]. Furthermore, the most recent systematic review, by Conforti et al., included a total of 38 randomized controlled trials in which patients were recruited according to the POSEIDON criteria. There was no evidence of benefit of standard management over CC co-treatment on either clinical pregnancy or live-birth rates in women with DOR, based on the available evidence, as shown in this POSEIDON-focused review [22]. Our conclusions are therefore concordant with this POSEIDON-specific evidence, and the inclusion of the broader, partly non-randomized literature did not alter that interpretation: the contribution of the non-randomized studies was to describe protocol variants not represented among the randomized trials rather than to modify the estimate of effect.
The applicability of these findings across the subgroups of low-prognosis patients nevertheless requires explicit qualification, since DOR and POR are not single entities. The evidence summarized here cannot be extrapolated equally to POSEIDON groups 1 and 2, in whom ovarian reserve markers are adequate and the low response is unexpected; to POSEIDON groups 3 and 4, in whom reserve markers are reduced and low response is predicted; to Bologna-defined poor responders, in whom a previous low response is a formal diagnostic requirement; or to women with DOR who have not previously undergone stimulation and in whom response is unknown. The obstacle is one of data rather than of interpretation: none of the studies included here reports outcomes stratified by POSEIDON group, and several define their populations by centre-specific criteria alone. Any subgroup-specific conclusion offered would therefore be inference rather than a finding of the evidence. What can be said is that the largest POSEIDON-specific synthesis available, comprising 38 randomized trials [22], and the broader synthesis presented here are concordant in finding no difference in live birth, and that the evidence base is weakest precisely where prognosis is poorest, in POSEIDON group 4. The value of the POSEIDON framework in standardizing low-prognosis populations, and the limitations that remain in its clinical application, have recently been reviewed in detail [42].
These findings are consistent with the randomized non-inferiority trial of Ragni et al., in which women with compromised ovarian reserve were allocated to stimulation with CC alone (150 mg/day, days 3–7) or to a short GnRH agonist protocol with recombinant FSH 450 IU daily [43]. Although the high-dose gonadotropin arm retrieved more oocytes and achieved embryo transfer more frequently, the delivery rate per started cycle did not differ significantly between the groups (3% vs. 5%, p = 0.77). It should be noted that this trial was terminated before the planned sample size was reached and was therefore underpowered, a limitation that recurs throughout this literature.

5.3. Potential Laboratory Benefits

Some studies have suggested a possible positive effect of CC on laboratory outcomes. Several have reported an increase in follicle number [38,40] or oocyte yield [30,38,39] in patients receiving CC in stimulated protocols. In addition, some studies have reported increases in the number of embryos or blastocysts obtained [32,38,40].
In a recently published study, Moffat et al. reported that significantly more blastocysts were generated using CC and low-dose gonadotrophin (150 IU/day) than with any other treatment group, despite a similar oocyte yield among all treatment groups. These findings could suggest that CC affects oocyte development and quality in addition to affecting the process of follicular recruitment, although this observation requires confirmation in larger studies [32]. The biological activity of CC may be mediated by an increase in endogenous gonadotropin release, thereby augmenting cohort recruitment and stimulation efficiency. In primate studies, intraovarian androgens influenced by the LH-stimulated theca cell have been shown to promote the growth of early follicles and increase FSH receptors on granulosa cells [20,21]. This synergistic action of androgens and FSH may be one reason supporting the gonadotropin-sparing effect and may also enhance follicular growth in cycles with CC. An alternative and equally plausible explanation for the blastocyst finding is that lower gonadotropin exposure itself is beneficial, by avoiding the recruitment of follicles containing developmentally incompetent oocytes and by limiting supraphysiological steroid concentrations during the follicular phase. The available data do not permit these two mechanisms to be distinguished. Moreover, these findings were mostly derived from small, single-centre cohorts and were not always associated with improved live-birth rates. Notably, Ochin et al. reported significantly higher oocyte yields and cumulative pregnancy rates with CC plus low-dose rFSH compared with a long GnRH agonist protocol. This study’s favourable outcomes have undergone significant criticism and should therefore be interpreted with caution [39].

5.4. Endometrial Effect

Although CC treatment is generally considered clinically neutral, some concerns have been raised about its anti-estrogenic effects on the endometrium. A thinner endometrium and lower implantation and pregnancy rates were found in the CC group compared with both antagonist- and agonist-based stimulation [31]. Moffat et al. also observed lower endometrial thickness in the CC-receiving groups [32]. Lu et al. provided further evidence in a large retrospective study of intrauterine insemination cycles, demonstrating that CC was associated with significantly thinner endometrium compared with gonadotropin-only cycles (median 6.8 vs. 8.3 mm, p < 0.001). Interestingly, in CC co-treated cycles endometrial thickness was positively associated with clinical and ongoing pregnancy rates, whereas no such association was observed in gonadotropin-only cycles [44]. As outlined in Section 2, this effect is a direct consequence of estrogen-receptor blockade and depletion in the endometrium, compounded by the prolonged persistence of the zuclomiphene isomer [24]. Consequently, monitoring of endometrial development in women treated with CC should be meticulous. In the event of suboptimal endometrial thickness, a segmented (freeze-all) strategy may be the better approach to minimize potential adverse effects on implantation and to allow embryo transfer in a subsequent cycle.

5.5. Cost, Treatment Burden and Patient-Centred Outcomes

Because CC does not improve live birth, its clinical justification rests largely on considerations of cost, tolerability and treatment burden—outcomes that are of considerable importance to patients but are inconsistently reported in the trials reviewed here.
The magnitude of the drug-cost saving is substantial. In the trial by Pilehvari et al., the minimal-stimulation arm used approximately 1760 IU less gonadotropin per cycle than the conventional arm [30], and pooled estimates indicate average reductions of 1700–2000 IU per cycle [16]. Given that gonadotropins represent the dominant pharmaceutical cost of an IVF cycle, this translates into a meaningful reduction in expenditure per initiated cycle. The economic analysis embedded within the trial of Ragni et al. is nevertheless instructive: although the CC arm was markedly less expensive per cycle, the mean estimated cost per delivery was 81,294 euros with CC compared with 113,107 euros with high-dose gonadotropins [43]. Both figures are strikingly high and illustrate that in women with compromised ovarian reserve the cost per live birth is driven overwhelmingly by the low absolute probability of success rather than by the price of the stimulation regimen. A cheaper cycle is therefore not automatically a cost-effective one, and cost per live birth rather than cost per cycle should be the metric of interest. Five economic endpoints must be kept distinct in this field: cost per initiated cycle, cost per oocyte, cost per embryo or blastocyst, cost per clinical pregnancy and cost per live birth. Only the last constitutes a formal measure of cost-effectiveness, and only a full economic evaluation can establish it; the data available for CC co-treatment address principally the first.
Beyond direct cost, CC-containing regimens reduce the number of subcutaneous injections and, in some protocols, the number of monitoring visits and the duration of stimulation [16,34]. In the “long CC” protocol described by Mandelbaum et al., continuous CC administration eliminated the need for a GnRH antagonist altogether while simultaneously reducing premature ovulation [33]. Mild-stimulation approaches have also been associated with better tolerance and lower treatment-related stress [45]. For couples self-funding treatment, or for those in whom repeated cycles are anticipated, these considerations may reasonably influence protocol selection even in the absence of a difference in live birth. Conversely, the higher cycle-cancellation rate observed with mild CC-based protocols in some studies—36.4% versus 12% in the trial of Siristatidis et al. [29]—represents a real burden of its own, and should be discussed explicitly with patients during counselling.

5.6. Clomiphene Citrate in the Context of Other Adjuvant Strategies

Clomiphene citrate is one of a number of adjuvant strategies proposed for poor responders, and its performance is best appraised comparatively.
Letrozole, a third-generation aromatase inhibitor, shares with CC the property of augmenting endogenous gonadotropin secretion, but achieves this by suppressing estradiol synthesis rather than by blocking estrogen receptors, and additionally raises intrafollicular androgen concentrations [19]. Randomized data comparing letrozole co-treatment with conventional antagonist protocols in Bologna-defined poor responders have generally shown reduced gonadotropin requirements without a significant improvement in pregnancy outcomes [46,47], mirroring the pattern observed with CC. A potential advantage of letrozole is the absence of the peripheral antiestrogenic effect on the endometrium, and comparative studies in gonadotropin-stimulated cycles have reported greater endometrial thickness with letrozole than with CC [19]. Adjunctive letrozole has also been incorporated into antagonist protocols specifically designed for poor responders [48]. The Cochrane review of oral agents combined with gonadotropins concluded that neither CC nor aromatase inhibitors improved live birth relative to conventional stimulation [41]. No head-to-head randomized comparison of CC with letrozole in women with DOR or POR was identified by our search; the comparison presented in this section is therefore indirect and is subject to the limitations attending all indirect comparison.
Androgen-based strategies have been explored on the basis of the same intraovarian rationale that underlies part of the CC effect. Transdermal testosterone pretreatment was shown in a randomized trial to improve the ovarian response to gonadotropins in low responders [49], and dehydroepiandrosterone, coenzyme Q10 and growth hormone have all been evaluated as adjuvants. Network meta-analyses of these interventions have generally found improvements in intermediate endpoints such as oocyte number or embryo quality, with inconsistent and low-certainty evidence regarding live birth [15]. In the network meta-analysis by Zhang et al., CC ranked lowest among ten interventions for clinical pregnancy [15]. It is important to interpret such rankings cautiously, since they are derived largely from small trials with heterogeneous populations and wide credible intervals.
Reflecting this overall uncertainty, the 2019 ESHRE guideline on ovarian stimulation concluded that none of the evaluated pre-treatments and adjuvant therapies could be recommended for the purpose of improving outcomes in poor responders; the 2025 update devotes particular attention to this question, and clinicians are advised to consult the current recommendations directly [23]. The 2025 update also moves away from the term poor response toward low response, in order to avoid implying prognosis from the response category alone; poor ovarian response is retained in this review for consistency with the terminology of the primary studies reported, while the shift is acknowledged, and predicted low response is distinguished from unexpected low response where the evidence permits. Substantively, the guideline states as a conditional recommendation, on moderate-to-low certainty evidence, that in predicted low responders CC alone, CC combined with gonadotropins, and gonadotropin stimulation alone are probably equally recommended [23]. This position is directly concordant with the principal conclusion of the present review, namely that CC co-treatment reduces gonadotropin exposure without evidence of a difference in live birth. The practical implication is that no adjuvant, including CC, can currently be offered to women with DOR on the basis of an expected improvement in live birth.

5.7. Alternative Stimulation Strategies

Because adjuvant pharmacotherapy has not resolved the problem of poor response, attention has increasingly shifted towards alternative stimulation architectures.
Mild stimulation, of which CC-based regimens are a principal example, has been evaluated extensively. In a systematic review and meta-analysis of randomized trials comparing mild (≤150 IU daily) with conventional stimulation, Datta et al. found no significant difference in live-birth rate in poor responders, together with lower cost and reduced risk of ovarian hyperstimulation syndrome [45]. Earlier randomized comparisons of mild and long protocols in women with expected poor responsiveness reached similar conclusions [50]. At the extreme of this spectrum, Lainas et al. compared modified natural cycle IVF with high-dose FSH stimulation in poor responders and reported comparable live-birth rates [51], reinforcing the observation that in this population the recruitable follicular cohort, rather than the intensity of stimulation, is the limiting factor.
The strategies considered in this section lie outside the central question of this review and are presented as the broader context of individualized treatment for low-prognosis patients, rather than as alternatives directly compared with CC co-treatment. Double stimulation in the follicular and luteal phases of the same cycle (DuoStim), originally described as the Shanghai protocol [52], allows two oocyte retrievals within a few weeks. Multicentre experience in poor-prognosis patients has shown that oocytes obtained after luteal-phase stimulation are of comparable developmental competence to those obtained in the follicular phase [53,54], and DuoStim may therefore shorten the time required to accumulate a sufficient cohort of oocytes or euploid blastocysts. Whether this efficiency advantage translates into higher cumulative live-birth rates than two consecutive conventional cycles remains uncertain.
Progestin-primed ovarian stimulation, in which an oral progestin replaces the GnRH antagonist for the prevention of a premature LH surge, offers a further patient-friendly and inexpensive option in a freeze-all setting; as reported by Liu et al., the addition of CC to a PPOS protocol further reduced gonadotropin consumption without altering reproductive outcomes [34]. Comparative studies of mild versus conventional stimulation in poor responders have likewise reported broadly equivalent clinical results [55].

5.8. Clinical Implications

Taken together, the evidence supports a pragmatic and individualized position. Clomiphene citrate co-treatment can be regarded as a legitimate option for women with DOR or POR, chosen not because it improves the probability of a live birth but because it achieves an equivalent probability at lower pharmaceutical cost and with a reduced injection burden. It is likely to be most attractive for patients who are self-funding treatment, who prioritize a less demanding regimen, or who are undergoing repeated cycles for oocyte or embryo accumulation. Where a fresh embryo transfer is planned, endometrial thickness should be monitored carefully and a freeze-all approach considered if development is suboptimal; where a segmented strategy is already intended, the endometrial disadvantage of CC becomes largely irrelevant. Conversely, CC should not be presented to patients as a means of improving their chance of a baby, and the possibility of a higher cycle-cancellation rate should be disclosed. Above all, realistic counselling regarding the low absolute live-birth rates achievable in this population remains more valuable than the choice between individual stimulation protocols.

6. Limitations

Several limitations of the current evidence base must be acknowledged. First, the included studies were of diverse designs (both randomized and observational) and varied widely in their stimulation protocols, gonadotropin doses, patient inclusion criteria, and primary outcomes. Second, and most importantly, most of the included studies were underpowered to detect clinically relevant differences in live-birth rates, which should be regarded as the most important, “gold-standard” clinical outcome in ART research; several trials, including that of Ragni et al., were terminated before reaching their planned sample size [43]. Third, population heterogeneity was a major issue: only four studies were RCTs [29,30,31,32], with a large variation in sample size (58 to 250 patients). Fourth, in several studies POR was defined by centre-specific criteria instead of standardized criteria such as the Bologna or POSEIDON criteria, which limits comparability across studies and impedes the application of findings to the POSEIDON subgroups most likely to benefit. Fifth, cumulative live-birth rate per started cycle—arguably the most meaningful endpoint in a population undergoing repeated treatment—was reported in only a minority of studies, and patient-centred outcomes such as treatment burden, tolerability and dropout were rarely quantified. Finally, a major limitation is that the present review was not registered in PROSPERO. In addition, a formal meta-analysis was not performed because of substantial clinical heterogeneity, and the review was restricted to publications in the English language, so that language and publication bias cannot be excluded. A further source of heterogeneity is aetiological rather than definitional: the designation of DOR encompasses women whose reduced reserve is idiopathic, age-related, iatrogenic or the consequence of ovarian surgery, and outcomes appear to differ accordingly, with impaired IVF outcomes and live-birth rates reported after endometrioma cystectomy compared with idiopathic DOR [56]. None of the studies included here stratifies its population in this way, so that the possibility that response to CC is modified by the underlying aetiology of reduced reserve cannot be examined and remains an open question; the disproportionate attrition between oocyte retrieval, blastocyst formation and the availability of a euploid embryo in the most severely affected groups [57] further limits the transferability of aggregate estimates to the individual patient. Lastly, the search was conducted with free-text terms alone and without controlled vocabulary, which constrains its exact reproducibility; references [42,56,57] postdate the closure of the search window and are cited for context only, without contributing to the evidence synthesis.

7. Conclusions

Combining CC with gonadotropins may be a reasonable alternative for women with POR: it reduces gonadotropin expenditure per initiated cycle and may reduce treatment burden, although its cost-effectiveness per live birth remains uncertain. Several studies have shown that CC reduces the total dose of gonadotropins required and shortens the duration of stimulation. Across mild, standard, and high-dose CC regimens, oocyte yield, clinical pregnancy rates, and live-birth rates were comparable to those obtained with conventional protocols. In this respect CC behaves similarly to letrozole and to the other adjuvants evaluated in this population: it modifies the treatment process without altering its outcome. Meaningful improvements in live-birth rates with current practice are rare, and close attention to endometrial development is warranted when a CC-based strategy is chosen. The principal value of CC therefore lies in reducing cost and treatment burden for a given probability of success, a trade-off that should be made explicit during patient counselling. Larger, well-powered, multicentre randomized controlled trials with cumulative live-birth rate as the primary endpoint, recruiting patients stratified according to the POSEIDON criteria and reporting economic and patient-centred outcomes alongside clinical ones, are needed to definitively establish the role of CC in the management of poor ovarian response.

Author Contributions

Conceptualization, M.P., M.B. and O.T.; methodology, M.P., M.B. and O.T.; software, M.P., M.B. and O.T.; validation, M.P., M.B. and O.T.; formal analysis, M.P., M.B. and O.T.; investigation, M.P., M.B. and O.T.; resources, M.P., M.B. and O.T.; data curation, M.P., M.B. and O.T.; writing—original draft preparation, M.P., M.B. and O.T.; writing—review and editing, M.P., M.B. and O.T.; visualization, F.V., N.V., A.L. and G.M.; supervision, F.V., N.V., A.L. and G.M.; project administration, F.V., N.V., A.L. and G.M. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable. This review is based solely on previously published studies and did not involve any new studies of human participants or animals performed by any of the authors.

Informed Consent Statement

Not applicable.

Data Availability Statement

Data sharing is not applicable to this article, as no new datasets were generated or analysed. All studies discussed are available in the cited published literature.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. World Health Organization. Infertility Prevalence Estimates, 1990–2021; World Health Organization: Geneva, Switzerland, 2023. [Google Scholar]
  2. Polyzos, N.P.; Devroey, P. A systematic review of randomized trials for the treatment of poor ovarian responders: Is there any light at the end of the tunnel? Fertil. Steril. 2011, 96, 1058–1061.e7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Drakopoulos, P.; Bardhi, E.; Boudry, L.; Vaiarelli, A.; Makrigiannakis, A.; Esteves, S.C.; Tournaye, H.; Blockeel, C. Update on the management of poor ovarian response in IVF: The shift from Bologna criteria to the Poseidon concept. Clin. Med. Insights Reprod. Health 2020, 14, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Galatis, D.; Kalopita, K.; Grypiotis, I.; Flessas, I.; Kiriakopoulos, N.; Micha, G. Researching the phenomenon of poor ovarian responders and management strategies in IVF: A narrative review. Acta Med. Acad. 2022, 51, 108–122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Ferraretti, A.P.; La Marca, A.; Fauser, B.C.J.M.; Tarlatzis, B.; Nargund, G.; Gianaroli, L.; on behalf of the ESHRE working group on Poor Ovarian Response Definition. ESHRE consensus on the definition of ‘poor response’ to ovarian stimulation for in vitro fertilization: The Bologna criteria. Hum. Reprod. 2011, 26, 1616–1624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Abu-Musa, A.; Haahr, T.; Humaidan, P. Novel physiology and definition of poor ovarian response; clinical recommendations. Int. J. Mol. Sci. 2020, 21, 2110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Humaidan, P.; Alviggi, C.; Fischer, R.; Esteves, S.C. The novel POSEIDON stratification of ‘Low prognosis patients in Assisted Reproductive Technology’ and its proposed marker of successful outcome. F1000Research 2016, 5, 2911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Alviggi, C.; Andersen, C.Y.; Buehler, K.; Conforti, A.; De Placido, G.; Esteves, S.C.; Fischer, R.; Galliano, D.; Polyzos, N.P.; Sunkara, S.K.; et al. A new more detailed stratification of low responders to ovarian stimulation: From a poor ovarian response to a low prognosis concept. Fertil. Steril. 2016, 105, 1452–1453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Esteves, S.C.; Conforti, A.; Sunkara, S.K.; Carbone, L.; Picarelli, S.; Vaiarelli, A.; Cimadomo, D.; Rienzi, L.; Ubaldi, F.M.; Zullo, F.; et al. Improving reporting of clinical studies using the POSEIDON criteria: POSORT guidelines. Front. Endocrinol. 2021, 12, 587051. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. La Marca, A.; Sunkara, S.K. Individualization of controlled ovarian stimulation in IVF using ovarian reserve markers: From theory to practice. Hum. Reprod. Update 2014, 20, 124–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Liu, Y.; Pan, Z.; Wu, Y.; Song, J.; Chen, J. Comparison of anti-Müllerian hormone and antral follicle count in the prediction of ovarian response: A systematic review and meta-analysis. J. Ovarian Res. 2023, 16, 117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Broer, S.L.; Mol, B.W.J.; Hendriks, D.; Broekmans, F.J.M. The role of antimullerian hormone in prediction of outcome after IVF: Comparison with the antral follicle count. Fertil. Steril. 2009, 91, 705–714. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Dewailly, D.; Andersen, C.Y.; Balen, A.; Broekmans, F.; Dilaver, N.; Fanchin, R.; Griesinger, G.; Kelsey, T.W.; La Marca, A.; Lambalk, C.; et al. The physiology and clinical utility of anti-Müllerian hormone in women. Hum. Reprod. Update 2014, 20, 370–385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Sunkara, S.K.; Rittenberg, V.; Raine-Fenning, N.; Bhattacharya, S.; Zamora, J.; Coomarasamy, A. Association between the number of eggs and live birth in IVF treatment: An analysis of 400 135 treatment cycles. Hum. Reprod. 2011, 26, 1768–1774. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Zhang, Y.; Zhang, C.; Shu, J.; Guo, J.; Chang, H.M.; Leung, P.C.K.; Sheng, J.-Z.; Huang, H. Adjuvant treatment strategies in ovarian stimulation for poor responders undergoing IVF: A systematic review and network meta-analysis. Hum. Reprod. Update 2020, 26, 247–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Youssef, M.A.F.; van Wely, M.; Mochtar, M.; Fouda, U.M.; Eldaly, A.; El Abidin, E.Z.; Elhalwagy, A.; Abdallah, A.A.M.; Zaki, S.S.; Ghafar, M.S.A.; et al. Low dosing of gonadotropins in in vitro fertilization cycles for women with poor ovarian reserve: Systematic review and meta-analysis. Fertil. Steril. 2018, 109, 289–301. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Kistner, R.W. Use of clomiphene citrate, human chorionic gonadotropin, and human menopausal gonadotropin for induction of ovulation in the human female. Fertil. Steril. 1966, 17, 569–583. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Bechtejew, T.N.; Nadai, M.N.; Nastri, C.O.; Martins, W.P. Clomiphene citrate and letrozole to reduce follicle-stimulating hormone consumption during ovarian stimulation: Systematic review and meta-analysis. Ultrasound Obstet. Gynecol. 2017, 50, 315–323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Haas, J.; Casper, R.F. In vitro fertilization treatments with the use of clomiphene citrate or letrozole. Fertil. Steril. 2017, 108, 568–571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Vendola, K.A.; Zhou, J.; Adesanya, O.O.; Weil, S.J.; Bondy, C.A. Androgens stimulate early stages of follicular growth in the primate ovary. J. Clin. Investig. 1998, 101, 2622–2629. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Weil, S.; Vendola, K.; Zhou, J.; Bondy, C.A. Androgen and follicle-stimulating hormone interactions in primate ovarian follicle development. J. Clin. Endocrinol. Metab. 1999, 84, 2951–2956. [Google Scholar] [CrossRef] [PubMed]
  22. Conforti, A.; Carbone, L.; Di Girolamo, R.; Iorio, G.G.; Guida, M.; Campitiello, M.R.; Ubaldi, F.M.; Rienzi, L.; Vaiarelli, A.; Cimadomo, D.; et al. Therapeutic management in women with a diminished ovarian reserve: A systematic review and meta-analysis of randomized controlled trials. Fertil. Steril. 2025, 123, 457–476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. The ESHRE Guideline Group on Ovarian Stimulation; Ata, B.; Bosch, E.; Broer, S.; Griesinger, G.; Grynberg, M.; Kolibianakis, E.; Kunicki, M.; La Marca, A.; Lainas, G.; et al. ESHRE guideline: Ovarian stimulation for IVF/ICSI: An update in 2025. Hum. Reprod. 2026, 41, 498–514. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. U.S. Food and Drug Administration. Clomid (Clomiphene Citrate Tablets USP) Prescribing Information; U.S. Food and Drug Administration: Silver Spring, MD, USA, 2017.
  25. Vendola, K.; Zhou, J.; Wang, J.; Bondy, C.A. Androgens promote insulin-like growth factor-I and insulin-like growth factor-I receptor gene expression in the primate ovary. Hum. Reprod. 1999, 14, 2328–2332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Page, M.J.; Moher, D.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. PRISMA 2020 explanation and elaboration: Updated guidance and exemplars for reporting systematic reviews. BMJ 2021, 372, n160. [Google Scholar] [CrossRef] [PubMed]
  28. Haddaway, N.R.; Page, M.J.; Pritchard, C.C.; McGuinness, L.A. PRISMA2020: An R package and Shiny app for producing PRISMA 2020-compliant flow diagrams, with interactivity for optimised digital transparency and Open Synthesis. Campbell Syst. Rev. 2022, 18, e1230. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Siristatidis, C.; Salamalekis, G.; Dafopoulos, K.; Basios, G.; Vogiatzi, P.; Papantoniou, N. Mild versus conventional ovarian stimulation for poor responders undergoing IVF/ICSI. In Vivo 2017, 31, 231–238. [Google Scholar] [CrossRef] [Scilit] [PubMed][Green Version]
  30. Pilehvari, S.; ShahrokhTehraninejad, E.; Hosseinrashidi, B.; Keikhah, F.; Haghollahi, F.; Aziminekoo, E. Comparison pregnancy outcomes between minimal stimulation protocol and conventional GnRH antagonist protocols in poor ovarian responders. J. Fam. Reprod. Health 2016, 10, 35–42. [Google Scholar]
  31. Schimberni, M.; Ciardo, F.; Schimberni, M.; Giallonardo, A.; De Pratti, V.; Sbracia, M. Short gonadotropin-releasing hormone agonist versus flexible antagonist versus clomiphene citrate regimens in poor responders undergoing in vitro fertilization: A randomized controlled trial. Eur. Rev. Med. Pharmacol. Sci. 2016, 20, 4354–4361. [Google Scholar] [PubMed]
  32. Moffat, R.; Hansali, C.; Schoetzau, A.; Ahler, A.; Gobrecht, U.; Beutler, S.; Raggi, A.; Sartorius, G.; De Geyter, C. Randomised controlled trial on the effect of clomiphene citrate and gonadotropin dose on ovarian response markers and IVF outcomes in poor responders. Hum. Reprod. 2021, 36, 987–997. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Mandelbaum, R.S.; Melville, S.; Masjedi, A.; Raj-Derouin, N.; Sriprasert, I.; Quinn, M.M.; Paulson, R.J.; Wilcox, J.G.; Guner, J.Z. Clomiphene citrate throughout the duration of ovarian stimulation in patients with diminished ovarian reserve: An approach to decrease costs, reduce injection burden, and prevent premature ovulation. J. Assist. Reprod. Genet. 2025, 42, 791–797. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Liu, A.; Li, J.; Shen, H.; Zhang, L.; Li, Q.; Zhang, X. Progestin-primed ovarian stimulation protocol with or without clomiphene citrate for poor ovarian responders: A retrospective cohort study. BMC Womens Health 2022, 22, 527. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Liu, S.; Liu, X.; Li, H.; Liu, M.; Lv, Y.; Li, Y. Clomiphene citrate priming increases sensitivity during ovarian stimulation in poor ovarian responders undergoing in vitro fertilization treatment: A retrospective cohort study. Hum. Fertil. 2023, 26, 1080–1086. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Sanverdi, I.; Kutlu, H.T.; Bilgic, B.E.; Incebiyik, A. A comparison of treatment results of the different treatment protocols in patients with poor ovarian response. Gynecol. Endocrinol. 2018, 34, 524–527. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Karakida, S.; Ezoe, K.; Fukuda, J.; Yabuuchi, A.; Kobayashi, T.; Kato, K. Effects of gonadotropin administration on clinical outcomes in clomiphene citrate-based minimal stimulation cycle IVF. Reprod. Med. Biol. 2020, 19, 128–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Triantafyllidou, O.; Sigalos, G.; Gkoles, L.; Kastora, S.; Vakas, P.; Batsiou, E.; Vlahos, N. The addition of clomiphene citrate to ovarian stimulation protocols for poor responders. Eur. J. Obstet. Gynecol. Reprod. Biol. 2020, 251, 136–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Ochin, H.; Ma, X.; Wang, L.; Li, X.; Song, J.; Meng, Y.; Shen, J.; Cui, Y.-G. Low-dose clomiphene citrate as a mild stimulation protocol in women with unsuspected poor in vitro fertilization result can generate more oocytes with optimal cumulative pregnancy rate. J. Ovarian Res. 2018, 11, 37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Hart, R.J. Stimulation for low responder patients: Adjuvants during stimulation. Fertil. Steril. 2022, 117, 669–674. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Kamath, M.S.; Maheshwari, A.; Bhattacharya, S.; Lor, K.Y.; Gibreel, A. Oral medications including clomiphene citrate or aromatase inhibitors with gonadotropins for controlled ovarian stimulation in women undergoing in vitro fertilisation. Cochrane Database Syst. Rev. 2017, 11, CD008528. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Carton, I.; Humaidan, P.; Midassi, H.; Alviggi, C.; Blockeel, C. Ten years of POSEIDON classification: A SOAR analysis. Reprod. Biol. Endocrinol. 2026, 24, 48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Ragni, G.; Levi-Setti, P.E.; Fadini, R.; Brigante, C.; Scarduelli, C.; Alagna, F.; Arfuso, V.; Mignini-Renzini, M.; Candiani, M.; Paffoni, A.; et al. Clomiphene citrate versus high doses of gonadotropins for in vitro fertilisation in women with compromised ovarian reserve: A randomised controlled non-inferiority trial. Reprod. Biol. Endocrinol. 2012, 10, 114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Lu, Y.; Cherouveim, P.; Jiang, V.; Dimitriadis, I.; James, K.E.; Bormann, C.; Souter, I. The impact of clomiphene citrate on the endometrium in comparison to gonadotropins in intrauterine insemination cycles: Is it thinner and does it matter? Front. Endocrinol. 2024, 15, 1414481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Datta, A.K.; Maheshwari, A.; Felix, N.; Campbell, S.; Nargund, G. Mild versus conventional ovarian stimulation for IVF in poor, normal and hyper-responders: A systematic review and meta-analysis. Hum. Reprod. Update 2021, 27, 229–253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Mohsen, I.A.; El Din, R.E. Minimal stimulation protocol using letrozole versus microdose flare up GnRH agonist protocol in women with poor ovarian response undergoing ICSI. Gynecol. Endocrinol. 2013, 29, 105–108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Ebrahimi, M.; Akbari-Asbagh, F.; Ghalandar-Attar, M. Letrozole + GnRH antagonist stimulation protocol in poor ovarian responders undergoing intracytoplasmic sperm injection cycles: An RCT. Int. J. Reprod. Biomed. 2017, 15, 101–108. [Google Scholar] [CrossRef] [Scilit]
  48. Schoolcraft, W.B.; Surrey, E.S.; Minjarez, D.A.; Stevens, J.M.; Gardner, D.K. Management of poor responders: Can outcomes be improved with a novel gonadotropin-releasing hormone antagonist/letrozole protocol? Fertil. Steril. 2008, 89, 151–156. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Fábregues, F.; Peñarrubia, J.; Creus, M.; Manau, D.; Casals, G.; Carmona, F.; Balasch, J. Transdermal testosterone may improve ovarian response to gonadotrophins in low-responder IVF patients: A randomized, clinical trial. Hum. Reprod. 2009, 24, 349–359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Revelli, A.; Chiadò, A.; Dalmasso, P.; Stabile, V.; Evangelista, F.; Basso, G.; Benedetto, C. “Mild” vs. “long” protocol for controlled ovarian hyperstimulation in patients with expected poor ovarian responsiveness undergoing in vitro fertilization (IVF): A large prospective randomized trial. J. Assist. Reprod. Genet. 2014, 31, 809–815. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  51. Lainas, T.G.; Sfontouris, I.A.; Venetis, C.A.; Lainas, G.T.; Zorzovilis, I.Z.; Tarlatzis, B.C.; Kolibianakis, E.M. Live birth rates after modified natural cycle compared with high-dose FSH stimulation using GnRH antagonists in poor responders. Hum. Reprod. 2015, 30, 2321–2330. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  52. Kuang, Y.; Chen, Q.; Hong, Q.; Lyu, Q.; Ai, A.; Fu, Y.; Shoham, Z. Double stimulations during the follicular and luteal phases of poor responders in IVF/ICSI programmes (Shanghai protocol). Reprod. Biomed. Online 2014, 29, 684–691. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  53. Vaiarelli, A.; Cimadomo, D.; Trabucco, E.; Vallefuoco, R.; Buffo, L.; Dusi, L.; Fiorini, F.; Barnocchi, N.; Bulletti, F.M.; Rienzi, L.; et al. Double stimulation in the same ovarian cycle (DuoStim) to maximize the number of oocytes retrieved from poor prognosis patients: A multicenter experience and SWOT analysis. Front. Endocrinol. 2018, 9, 317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  54. Cimadomo, D.; Vaiarelli, A.; Colamaria, S.; Trabucco, E.; Alviggi, C.; Venturella, R.; Alviggi, E.; Carmelo, R.; Rienzi, L.; Ubaldi, F.M. Luteal phase anovulatory follicles result in the production of competent oocytes: Intra-patient paired case-control study comparing follicular versus luteal phase stimulations in the same ovarian cycle. Hum. Reprod. 2018, 33, 1442–1448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  55. Yoo, J.H.; Cha, S.H.; Park, C.W.; Kim, J.Y.; Yang, K.M.; Song, I.O.; Koong, M.K.; Kang, I.S.; Kim, H.O. Comparison of mild ovarian stimulation with conventional ovarian stimulation in poor responders. Clin. Exp. Reprod. Med. 2011, 38, 159–163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  56. Kobayashi, M.; Asada, Y.; Sugishita, Y.; Osuka, S.; Kitajima, M.; Kawamura, K.; Shirasawa, H.; Tsuzuki-Nakao, T.; Yamada, M.; Takai, Y.; et al. Impact of the etiology of diminished ovarian reserve on assisted reproductive technology outcomes: A multicenter retrospective cohort study. J. Obstet. Gynaecol. Res. 2026, 52, e40718. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  57. Wyroba, J.; Barszcz, M.; Fajt, I.; Kochan, J. PGT-A in POSEIDON patients—Perspectives and limitations. JBRA Assist. Reprod. 2025, 29, 608–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. PRISMA 2020 flow diagram of study identification, screening, eligibility assessment, and inclusion.
Reprodmed 07 00044 g001
Table 1. Comparison of the Bologna and POSEIDON classification systems for poor ovarian response and low prognosis.
FeatureBologna Criteria (ESHRE, 2011) [5]POSEIDON Criteria (2016) [7,8]
Underlying conceptBinary definition of “poor ovarian response”Graded concept of “low prognosis” in ART
Diagnostic requirementAt least two of three criteria: (i) age ≥ 40 years or another risk factor; (ii) previous POR (≤3 oocytes with a conventional protocol); (iii) abnormal ovarian reserve test (AFC < 5–7 or AMH < 0.5–1.1 ng/mL)Stratification by age (<35 vs. ≥35 years), ovarian reserve markers (AFC <5, AMH <1.2 ng/mL) and previous ovarian response
SubgroupsNone; single categoryGroup 1: <35 years, adequate markers, unexpected poor/suboptimal response; Group 2: ≥35 years, adequate markers, unexpected poor/suboptimal response; Group 3: <35 years, reduced markers; Group 4: ≥35 years, reduced markers
Therapeutic endpointNot explicitly definedNumber of oocytes required to obtain at least one euploid blastocyst for the individual patient
Principal strengthImproved consistency and comparability of research populationsPatient-oriented; distinguishes expected from unexpected poor response and separates quantitative from age-related (qualitative) limitation
Principal limitationAggregates biologically heterogeneous patients; limited value for individualized decision-making [6]Requires cumulative outcome data and standardized reporting (POSORT) [9]; prognostic thresholds still under validation
AFC, antral follicle count; AMH, anti-Müllerian hormone; ART, assisted reproductive technology; ESHRE, European Society of Human Reproduction and Embryology; POR, poor ovarian response; POSEIDON, Patient-Oriented Strategies Encompassing Individualized Oocyte Number; POSORT, POSEIDON Study Reporting.
Table 2. Characteristics and main outcomes of studies evaluating clomiphene citrate plus gonadotropins in women with diminished ovarian reserve or poor ovarian response.
StudyDesign/NPOR
Criteria
ProtocolKey OutcomesGonadotropin
Data
Conclusions
Siristatidis et al., 2017 [29]RCT
n = 58
Bologna criteriaMild: CC 100 mg (d2–6) + cetrorelix 0.25 mg + rFSH 150 IU/d (n = 33)
vs.
Conventional: long GnRH-a or antagonist + 300–450 IU/d (n = 25)
COCs: 1.0 (0–4) vs. 3.0 (0–8.4), p < 0.001
MII oocytes: 1.0 vs. 2.0, p = 0.001
EMT: 7.8 vs. 10.0 mm, p = 0.015
Cancellation: 36.4% vs. 12%, p = 0.036
CPR: 12.1% vs. 20%, p = 0.412
LBR: 9.1% vs. 12%, p = 0.719
Miscarriage: 40% vs. 40%, p = 1.0
Total Gn: 1050 vs. 4040 IU, p < 0.001
Duration: 11.0 vs. 12.0 d, p = 0.140
CC-based mild stimulation reduces Gn use but yields fewer oocytes; CPR and LBR not significantly different from conventional protocols
Pilehvari et al., 2016 [30]RCT
n = 80
POR (centre criteria)Mild: CC 100 mg + hMG 150 IU/d + GnRH antagonist (n = 40)
vs.
Conventional: hMG 300 IU/d + GnRH antagonist (n = 40)
Oocytes retrieved: similar between groups
CPR: comparable (NS)
Total Gn dose: significantly lower with CC
Similar pregnancy rates with lower cost
Total Gn: significantly lower with CC (p < 0.05)Mild CC protocol provides comparable outcomes with significantly reduced cost and medication exposure
Schimberni et al., 2016 [31]RCT
n = 250
POR in previous IVF cycle (≤3 oocytes)Group A: CC 100 mg + high-dose FSH + antagonist (n = 68)
vs.
Group B: FSH + flexible antagonist (n = 71)
vs.
Group C: FSH + short GnRH agonist (n = 75)
CPR: 5.9% vs. 14.1% vs. 29.3%, p = 0.028
Implantation rate: 4.8% vs. 9.3% vs. 19.2% (CC vs. antagonist p = 0.040; CC vs. agonist p = 0.003)
Oocytes retrieved: NS between groups
Embryos transferred: NS
EMT: thinner in CC group
Total FSH: NS between groups
Duration: NS
CC performed worst among protocols; short GnRH agonist should be preferred. CC associated with thinner endometrium and lower implantation
Moffat et al., 2021 [32]RCT (double-blind)
n = 114
Bologna criteria (≥2 of 3 criteria)
Median age 38.5 y
2 × 2 factorial design:
A: CC 100 mg (d3–7) + 450 IU HMG (n = 28)
B: CC 100 mg + 150 IU HMG (n = 29)
C: Placebo + 450 IU HMG (n = 30)
D: Placebo + 150 IU HMG (n = 27)
All: GnRH antagonist protocol
Oocytes: A 2.85, B 4.32, C 3.33, D 3.22 (p = 0.246, NS)
Blastocysts: B 1.77 vs. A 0.83 (p = 0.006)
EMT: lower in CC groups
Overall LBR: 12.3%
Cumulative LBR: 14.7%
FSH serum: lower in 150 IU groups
By design: 150 vs. 450 IU
CC did not affect serum FSH levels
CC + low-dose Gn (150 IU) yielded significantly more blastocysts. CC may improve oocyte competence rather than yield. LBR comparable across arms
Mandelbaum et al., 2025 [33]Retrospective cohort
n = 469 cycles
DOR (centre criteria; AMH-based)Long CC: CC throughout stimulation (no GnRH antagonist) + high-dose rFSH (n = 361)
vs.
5-day CC + GnRH antagonist + high-dose rFSH (n = 108)
MII oocytes: median 5 vs. 4.5, p = 0.922
MII/AFC ratio: 0.69 vs. 0.56, p = 0.16
Premature ovulation: 0.3% vs. 3.0%, p = 0.019
Age and AMH similar between groups
Both groups: high-dose rFSH
Long CC eliminates need for antagonist
Long CC is a feasible, patient-friendly alternative that prevents premature ovulation without antagonist injections; non-inferior MII yield
Liu A et al., 2022 [34]Retrospective cohort
n = 578
Bologna criteria (POR)Group A: PPOS (HMG 300 IU/d + MPA 10 mg/d)
vs.
Group B: PPOS + CC 50 mg/d
Oocytes retrieved: lower in CC group (p < 0.001)
Oocyte retrieval rate: NS
Maturation rate: NS
Fertilization rate: NS
Viable embryo rate: NS
CPR: OR 1.286 (95% CI 0.671–2.470)
LBR: OR 1.390 (95% CI 0.478–3.990)
LH on trigger day: higher with CC (p < 0.001)
Total HMG: 2999 vs. 3399 IU, p < 0.001
Duration: 10.2 vs. 11.3 d, p < 0.001
Adding CC to PPOS lowers Gn dose and duration but does not improve CPR or LBR in POR
Liu S et al., 2023 [35]Retrospective cohort
n = 294 (374 cycles)
Bologna criteria (POR)CC priming: CC + low-dose Gn + GnRH antagonist (n = 193 cycles)
vs.
Classical flexible GnRH antagonist protocol (n = 181 cycles)
FOI: significantly higher in CC group
Gn dosage per follicle: significantly lower
Cumulative ongoing PR: aOR 0.761 (95% CI 0.300–1.933, p = 0.566)
Age, BMI, Gn/follicle, FOI negatively associated with outcomes
Total Gn: significantly lower
Gn/follicle: lower
Duration: shorter
CC priming increases ovarian sensitivity (higher FOI, lower Gn per follicle) without compromising cumulative ongoing PR
Sanverdi et al., 2018 [36]Retrospective cohort
n = 214
POR history (≤3 oocytes or cycle cancellation)Group 1: Gn 450 IU + GnRH antagonist (n = 77)
vs.
Group 2: Gn 450 IU + microdose GnRH-a (n = 84)
vs.
Group 3: CC 100 mg/d + Gn 300 IU + antagonist (n = 53)
Oocytes: Group 1 > Groups 2 and 3 (p significant)
MII oocytes: Group 1 superior
Embryos: Group 1 superior
CPR: highest in Group 3 (NS)
No significant difference in CPR between groups
Total Gn: significantly lower in Group 3 (p < 0.001)CC reduces Gn consumption but does not improve key reproductive outcomes vs. high-dose stimulation
Karakida et al., 2020 [37]Retrospective (propensity score matched)
n = 446
Minimal stimulation population (serum FSH-based)CC 50 mg/d + EGn (75–150 IU if FSH < 15) (CC-EGn, n = 223)
vs.
CC 50 mg/d alone (CC, n = 223)
(Propensity score matched 1:1)
Retrieved oocytes: higher in CC-EGn
Fertilized oocytes: higher in CC-EGn
Cleaved embryos: higher in CC-EGn
Cryopreserved blastocysts: higher in CC-EGn
Cumulative LBR: comparable (OR 1.193 vs. 1.553 per oocyte)
EGn added only if FSH < 15:
75 IU (FSH 10–15)
150 IU (FSH < 10)
EGn supplementation increases oocyte yield but not cumulative LBR; start with CC only and add EGn if endogenous Gn insufficient
Triantafyllidou et al., 2020 [38]Prospective cohort
n = 12 (crossover)
Bologna criteria (POR with previous failed IVF)Cycle 1: hMG 300 IU/d + GnRH antagonist (hMG group)
vs.
Cycle 2: CC 100 mg (d3–7) + hMG 300 IU/d + GnRH antagonist (CC-hMG group)
(Same patients, sequential cycles)
E2 levels: significantly higher with CC (p < 0.05)
Follicles: significantly more with CC (p < 0.05)
Oocytes: significantly more with CC (p < 0.05)
Embryos: significantly more with CC (p < 0.05)
Cancellation: significantly lower with CC
CPR: 2 clinical pregnancies → 2 live births (CC-hMG)
3 biochemical pregnancies (CC-hMG)
Both groups: hMG 300 IU/d (identical dose)CC addition to high-dose hMG enhances laboratory response but small sample size precludes conclusions on clinical outcomes
Ochin et al., 2018 [39]Retrospective (before–after)
n = 65 (130 cycles)
Unsuspected poor IVF result (predicted normal responders)Cycle 1 (Group 1): Long GnRH-a + high-dose Gn (≥150 IU/d)
vs.
Cycle 2 (Group 2): CC 50 mg + low-dose rFSH (75–112.5 IU/d)
(Same patients, sequential cycles)
Oocytes: 7.26 ± 1.95 vs. 5.98 ± 1.31, p = 0.03
Cumulative PR: 51% vs. 9.2%, p < 0.0001
Patients without embryos: 12.3% vs. 33.9%, p < 0.0001
Note: crossover design, different protocol types
Total rFSH: significantly lower in CC group (75–112.5 vs. ≥150 IU/d)CC + low-dose rFSH yielded more oocytes and better cumulative PR, but before–after design and different protocol types limit generalizability
AFC, antral follicle count; AMH, anti-Müllerian hormone; aOR, adjusted odds ratio; BMI, body mass index; CC, clomiphene citrate; CI, confidence interval; COC, cumulus-oocyte complex; CPR, clinical pregnancy rate; d, day; DOR, diminished ovarian reserve; E2, estradiol; EGn, exogenous gonadotropin; EMT, endometrial thickness; FOI, follicle-to-oocyte index; FSH, follicle-stimulating hormone; Gn, gonadotropin; GnRH, gonadotropin-releasing hormone; GnRH-a, GnRH agonist; hMG/HMG, human menopausal gonadotropin; IU, international units; IVF, in vitro fertilization; LBR, live-birth rate; LH, luteinizing hormone; MII, metaphase II; MPA, medroxyprogesterone acetate; NS, not significant; OR, odds ratio; POR, poor ovarian response; PPOS, progestin-primed ovarian stimulation; PR, pregnancy rate; RCT, randomized controlled trial; rFSH, recombinant FSH; vs., versus.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.