


Highlights
What are the main findings?
- Over 30 years, there has been a gradual decline in pediatric hospitalizations for acute asthma exacerbations in a Tertiary Hospital in Beijing. The highest number of hospitalizations occurred in 1990 (93 patients, 8.4%), while the lowest coincided with the COVID-19 pandemic in 2020 (16 patients, 1.4%).
- Hospitalizations peaked in autumn, especially in October (13.29%), and were most common among preschool-age children (46.75%).
What are the implications of the main findings?
- The decline in hospitalizations suggests that childhood asthma prevention and control measures have led to improvements in asthma management.
- Further efforts are needed to enhance asthma prevention and management strategies, particularly for high-risk groups and during peak seasons, to reduce acute exacerbations and hospitalizations.
Abstract
Objectives: To provide an evidence-based reference for preventing and managing pediatric acute asthma exacerbations by examining epidemiology and long-term trends of hospitalized cases in a tertiary hospital in Beijing over 30 years. Methods: Retrospective analysis of clinical data from children hospitalized for acute asthma exacerbation at Peking University Third Hospital from 1994 to 2023. Data collected included demographics, onset timing, and hospital stay duration, with distribution patterns analyzed across ages, years, seasons, and months. Results: The study included 1106 patients (65.73% male, 34.27% female) with a median age of 4 years. Hospitalizations peaked in 1999 (8.40%) and declined, reaching the lowest point in 2020 (1.45%) coinciding with the COVID-19 pandemic. Most admissions occurred in autumn (34.27%), especially in October (13.29%). The average hospital stay was 5.35 ± 2.65 days, longest for toddlers. Conclusions: Over 30 years, pediatric hospitalizations for acute asthma exacerbations in this tertiary center have shown a declining trend, suggesting improved asthma management. However, the persistent autumn peak and male predominance highlight the need for targeted prevention strategies—particularly for male and preschool-aged children before the autumn school term—to further reduce acute exacerbations and hospitalizations.
1. Introduction
Asthma is the most prevalent chronic respiratory condition that is not caused by infection in childhood. Over the past three decades, rapid industrialization has significantly altered lifestyles and living environments, contributing to a notable increase in childhood asthma prevalence nationwide. Meanwhile, diagnostic and management standards have also improved markedly. Consistent with global epidemiological trends, childhood asthma prevalence has increased steadily both domestically and internationally [1,2]. Asthma exerts multifaceted adverse effects on pediatric health, compromising physical growth and development, impairing psychological well-being, and imposing substantial economic burdens on families and society at large [3].
The pathogenesis of bronchial asthma is a highly complex process; increasing evidence indicates that asthma results from the combined effects of genetic and environmental factors [4]. Acute exacerbations of asthma are the leading reason for hospital admissions among children with this condition, with approximately 17% of pediatric patients with asthma requiring inpatient management [5]. Many risk factors can cause acute exacerbation of asthma, including allergens, viral infections, pollutants, tobacco smoke, and medications. Reducing children’s exposure to risk factors can improve asthma control and decrease the need for therapeutic medications. However, environmental conditions, climate, and demographic characteristics vary significantly by region. As the capital of China, Beijing faces unique geographical challenges, including high air pollution, which makes epidemiological analysis of asthma in this region particularly important. Therefore, assessing the etiological factors underlying acute exacerbation of asthma and reducing the hospitalization rate related to such episodes are critical for lowering the morbidity and mortality of childhood asthma.
Based on this, this study conducted a retrospective analysis of the clinical data of children aged 1–15 years who were hospitalized due to acute asthma exacerbation in a tertiary hospital in Beijing from 1994 to 2023. The primary goal was to investigate the clinical characteristics of these patients and to provide evidence-based resources for the prevention, treatment, and long-term management of acute asthma exacerbation in childhood in Beijing. The findings are reported as follows.
2. Materials and Methods
2.1. General Information
This study included 1106 children aged 1–15 years with acute asthma exacerbation admitted from January 1994 to December 2023 to the Department of Pediatrics, Peking University Third Hospital. Based on age, the patients were stratified into the following three groups: toddlerhood (1 ≤ age < 3 years), preschool age (3 ≤ age < 7 years), and school age (7 ≤ age < 15 years).
It was infeasible to conduct informed consent notification and obtain signed informed consent forms, as this study is a retrospective analysis based on clinical medical record data with an extended time span. The need for signing relevant informed consent forms was waived on the premise of maximizing the protection of patients’ rights, interests, and privacy, following submission to and review by the Medical Ethics Committee of Peking University Third Hospital. Ethics Approval Number: M20250542.
2.2. Inclusion and Exclusion Criteria
Inclusion criteria were as follows: (1) Pediatric inpatients who met the diagnostic criteria for childhood asthma issued in China across different eras [6,7,8,9,10]; (2) those aged 1 to 15 years old (inclusive of 1 and 15 years old); and (3) those with complete medical records.
Exclusion criteria were as follows: (1) Children with asthma in the clinical remission or chronic persistent phase; (2) children who have enrolled multiple times during the same acute exacerbation phase; (3) those with specific respiratory system diseases such as bronchial foreign bodies, respiratory tract malformations, lung tumors, or lung trauma; and (4) those with severe diseases involving other systems including the heart, brain, liver, gastrointestinal tract, and kidneys.
2.3. Methods
This study analyzed demographic (age, gender, date of birth) and clinical data (visit year, visit season, visit month, length of hospital stay) from 1994 to 2023 of hospitalized children aged 1–15 years with acute asthma exacerbation. The gender distribution of the children was specifically examined, and the distribution characteristics by different years, seasons, months, and lengths of hospital stay were also assessed.
2.4. Statistical Methods
SPSS 24.0 software was used for statistical data analysis. Descriptive analysis was employed to examine the general demographic characteristics of hospitalized children with acute asthma exacerbation. Measurement data conforming to normal distribution were expressed as mean ± standard deviation ( ± SD); for those not conforming to normal distribution, median and interquartile range were used. T-test and one-way analysis of variance (ANOVA) were commonly used for assessing measurement data, while chi-square test (χ2 test) and rank sum test were used for analyzing count data. The statistical significance was set at p < 0.05.
3. Results
3.1. Gender Distribution of Hospitalized Children with Acute Asthma Exacerbation
This study enrolled 1106 hospitalized children with acute asthma exacerbation, consisting of 727 males (65.73%) and 379 females (34.27%).
3.2. Age (Group) Distribution of Hospitalized Children with Acute Asthma Exacerbation
The median age of hospitalized children with acute asthma exacerbation in this study was 4 years (interquartile range, IQR: 2–7). The participants were stratified into the following three age groups: toddlerhood (1 ≤ age < 3 years), preschool age (3 ≤ age < 7 years), and school age (7 ≤ age < 15 years), with 306, 517, and 283 cases, respectively. The preschool age group accounted for approximately half of the total cohort, which is the highest proportion (46.75%), followed by the toddlerhood group, which constituted more than a quarter (27.67%) of the patients.
3.3. Gender Differences in Hospitalized Children with Acute Asthma Exacerbation Across Different Age Groups
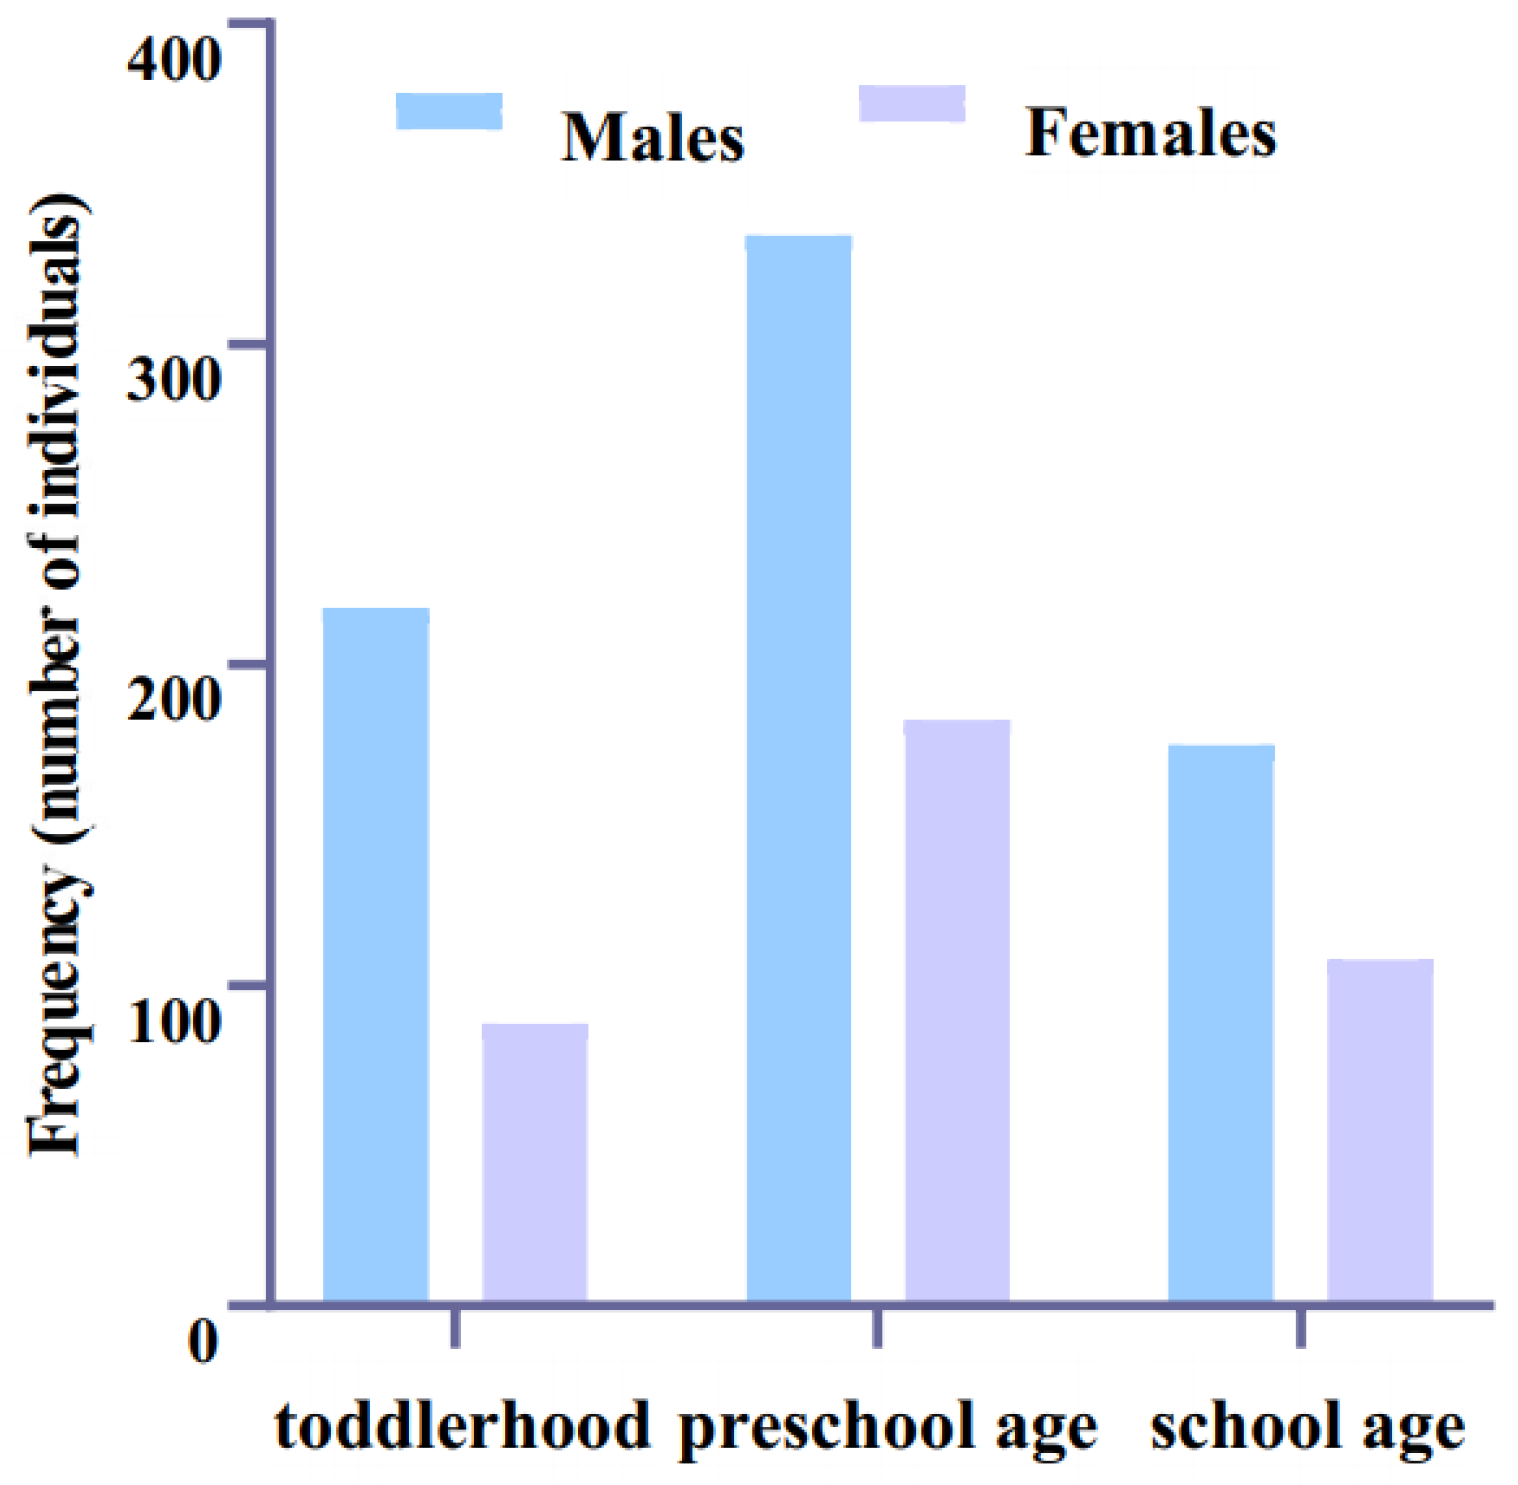
The number of male hospitalized children with acute asthma exacerbation was consistently higher than that of females across all age groups. Specifically, the male-to-female ratio was approximately 2.5:1 (218 vs. 88), 1.8:1 (334 vs. 183), and 1.6:1 (175 vs. 108) in the toddlerhood, preschool age, and school age groups, respectively. Figure 1 illustrates these gender disparities across age strata.
Figure 1.
Gender disparities in hospitalized children with acute asthma exacerbation among different age groups.
Males were more predominant than females across all age groups, with gender disparities diminishing with increasing age. A significant difference in gender distribution among the three groups (χ2 = 6.322, p < 0.05; Table 1) was exhibited through statistical analysis. Post hoc pairwise comparisons showed no significant differences between toddlerhood and preschool age (χ2 = 3.836, p = 0.05) or between preschool and school age (χ2 = 0.605, p = 0.437). However, a remarkable difference was noted between toddlerhood and school age (χ2 = 5.856, p = 0.016).
Table 1.
Comparison of gender disparities in hospitalized children with acute asthma exacerbation across different age groups.
3.4. Annual Distribution of Hospitalized Children with Acute Asthma Exacerbation
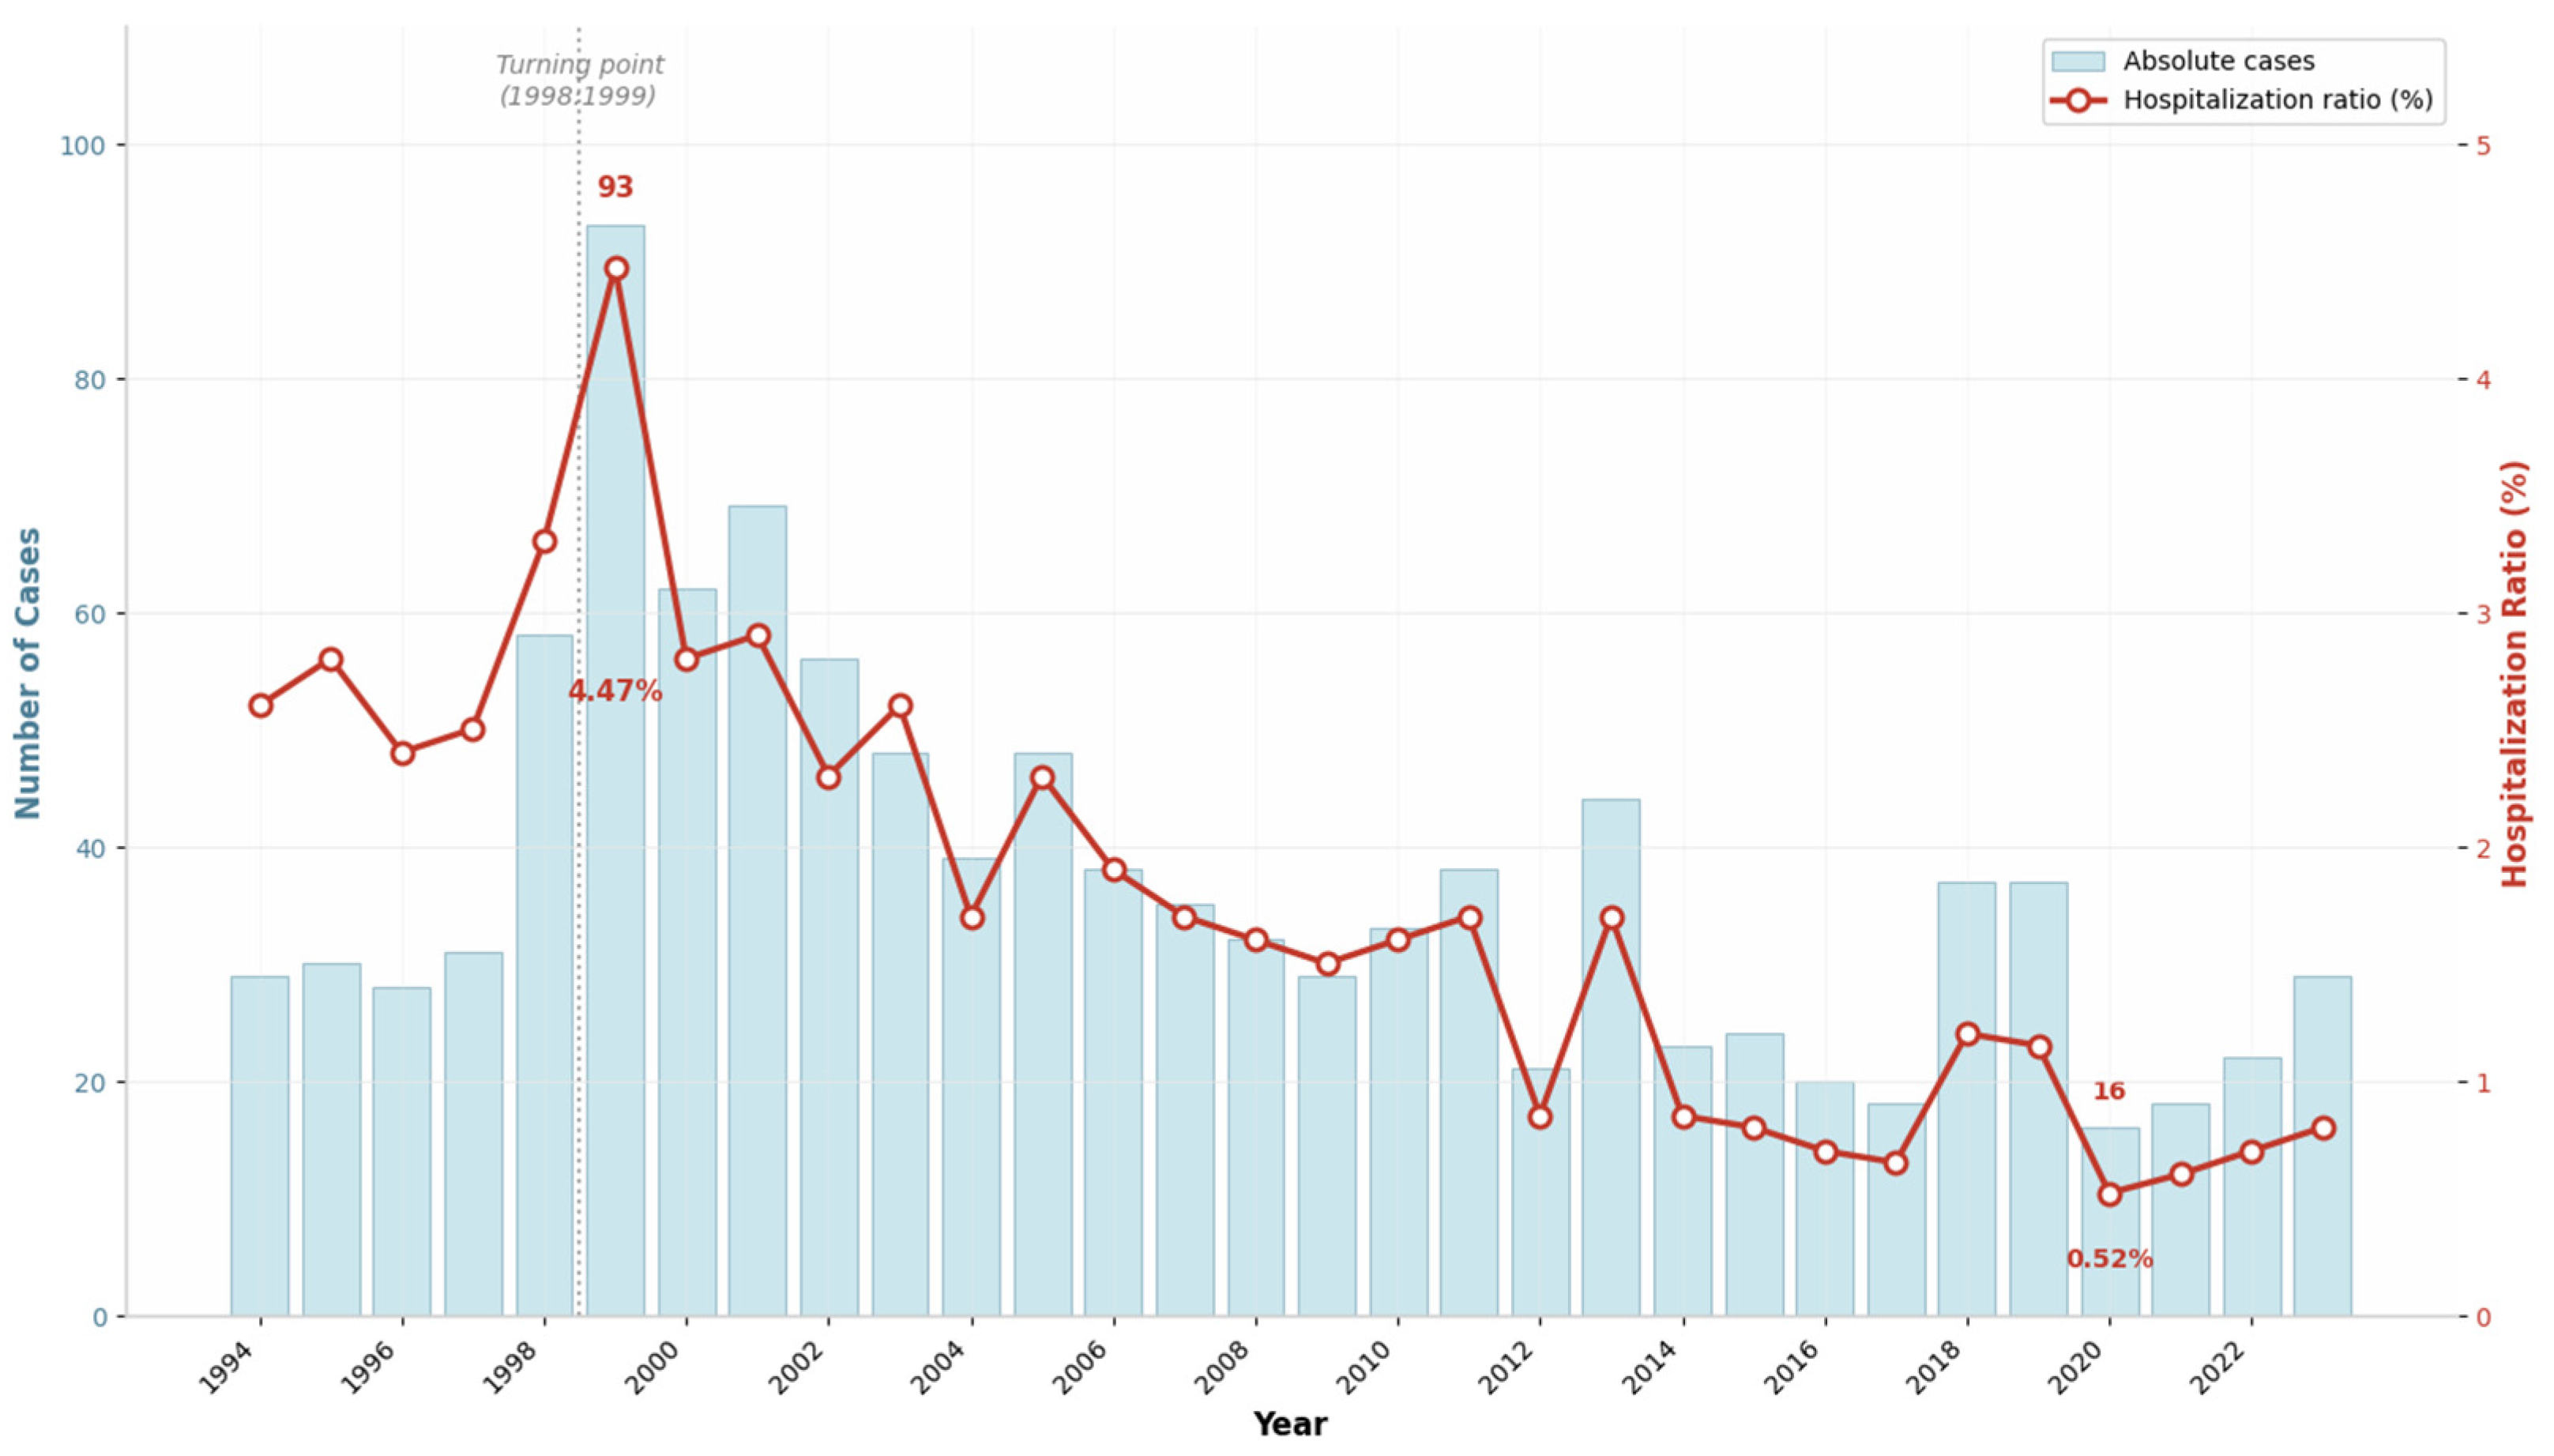
From 1994 to 2023, 1106 children with acute asthma exacerbation were admitted to Peking University Third Hospital. The asthma hospitalization ratio (asthma cases/total pediatric discharges) peaked in 1999 at 4.47% (93 cases), the highest proportion in the 30-year series (1.74% ± 0.96%). Between 1994 and 1997, both absolute admissions and hospitalization ratios remained relatively stable, followed by a significant increase in 1998 and the 1999 peak. After 2000, the hospitalization ratio showed a significant downward trend, with two minor peaks in 2013 (1.56%) and 2018–2019 (1.10–1.14%). In 2020, admissions dropped to their lowest level (16 cases, 0.78%), coinciding with the COVID-19 pandemic, followed by a slow recovery through 2023 (29 cases, 0.75%). The annual admission figures and hospitalization ratios are illustrated in Figure 2.
Figure 2.
Annual pediatric asthma admissions and hospitalization ratios at Peking University Third Hospital (1994–2023).
3.5. Monthly Variation in Admissions
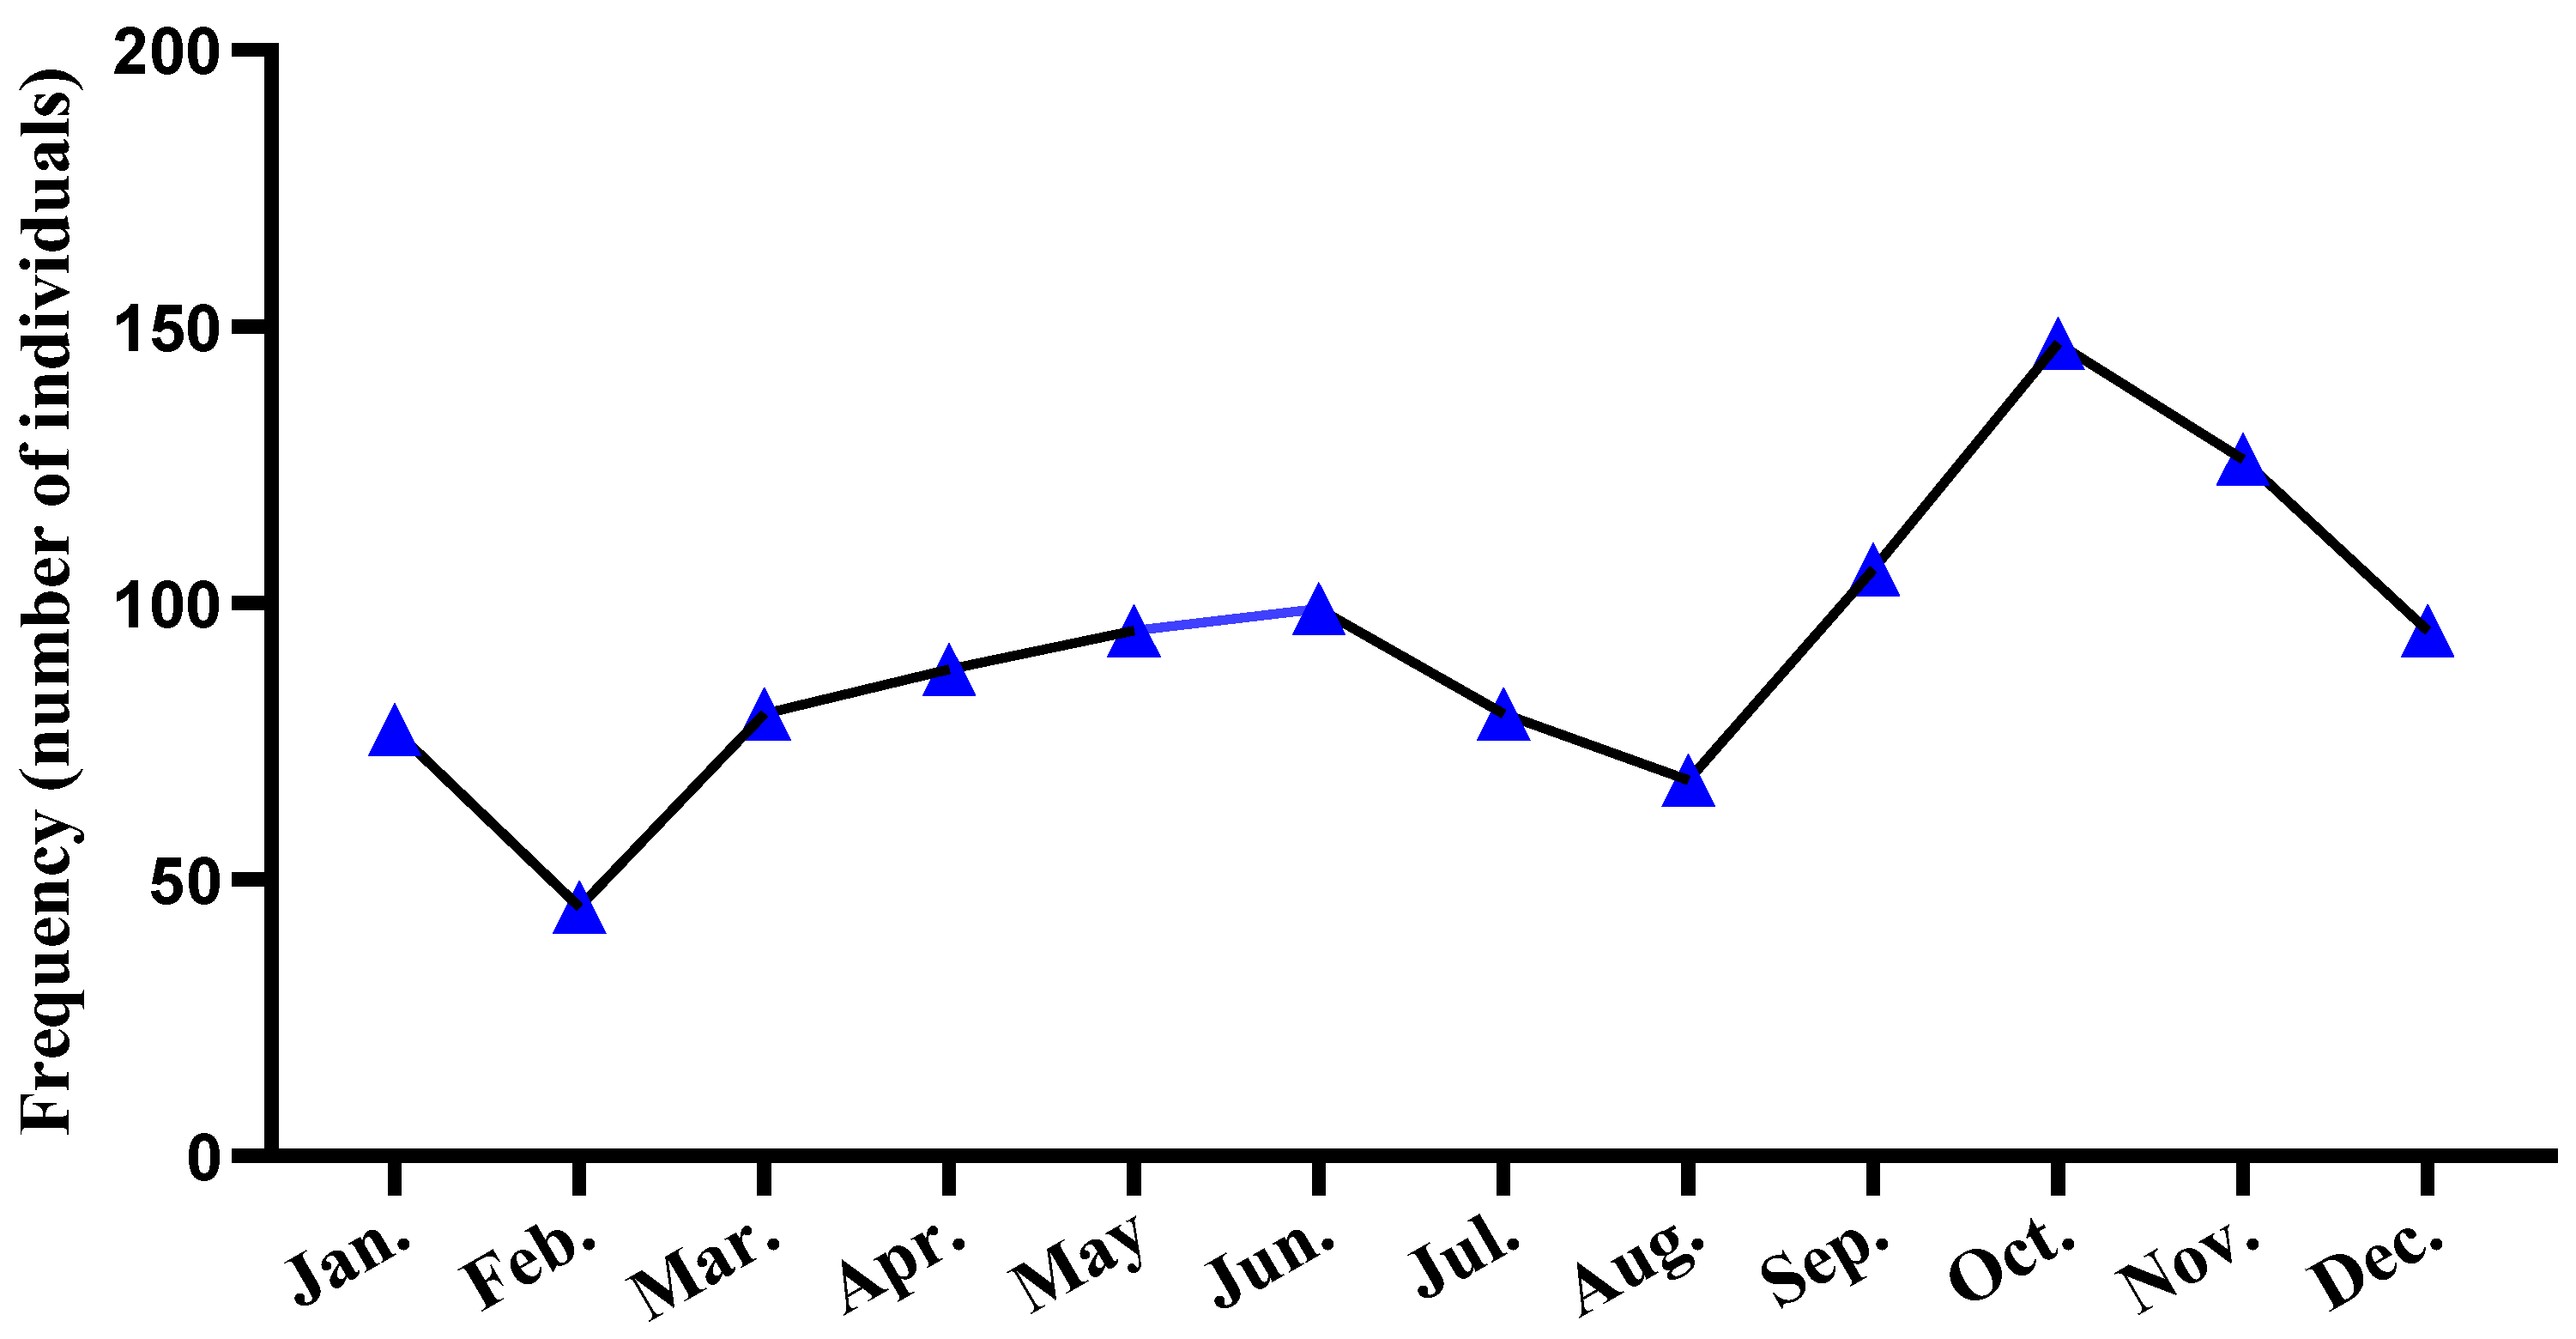
Figure 3 illustrates the monthly distribution of hospitalized children with acute asthma exacerbation at Peking University Third Hospital between 1994 and 2023. The highest monthly admission volume was in October (147 cases, 13.29%), followed by November (126 cases, 11.39%) and September (106 cases, 9.58%). In contrast, February had the lowest reported number of admissions (45 cases, 4.06%).
Figure 3.
Monthly distribution of hospitalized children with acute asthma exacerbation.
3.6. Seasonal Patterns of Admissions
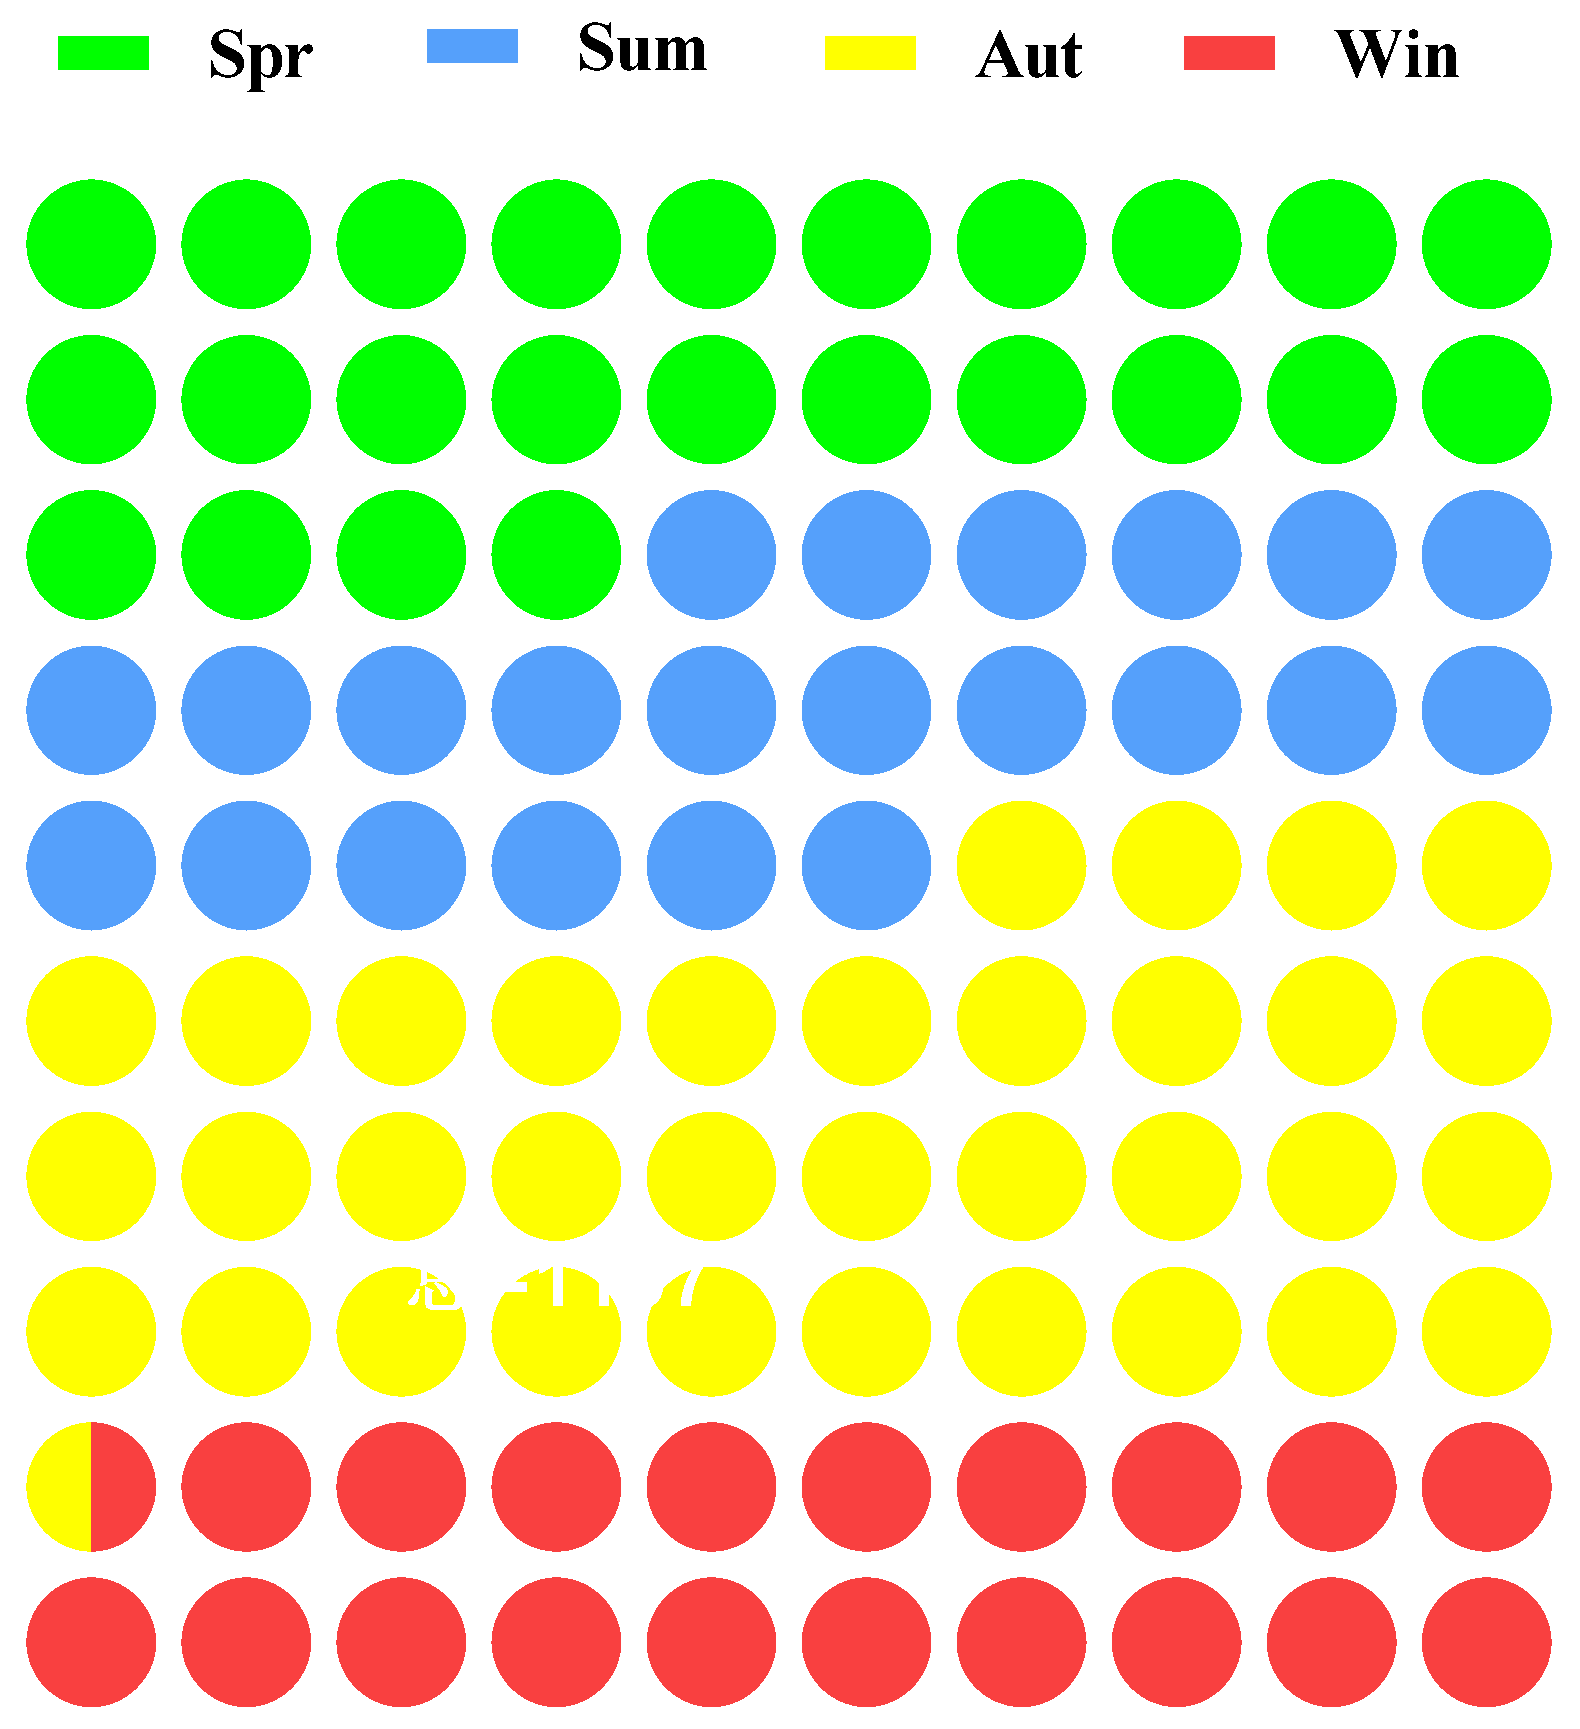
Hospitalized children admitted to Peking University Third Hospital between 1994 and 2023 owing to acute asthma exacerbation were categorized according to season based on meteorological standards as follows: spring (March–May), summer (June–August), autumn (September–November), and winter (December–February of the following year). As illustrated in Figure 4, autumn was consistently the peak season for admissions. The number of hospitalized patients in each season was as follows: spring, 263 cases (23.78%); summer, 247 cases (22.33%); autumn, 379 cases (34.27%); and winter, 217 cases (19.62%).
Figure 4.
Seasonal distribution of hospitalized children with acute asthma exacerbation.
3.7. Age-Related Seasonal Patterns
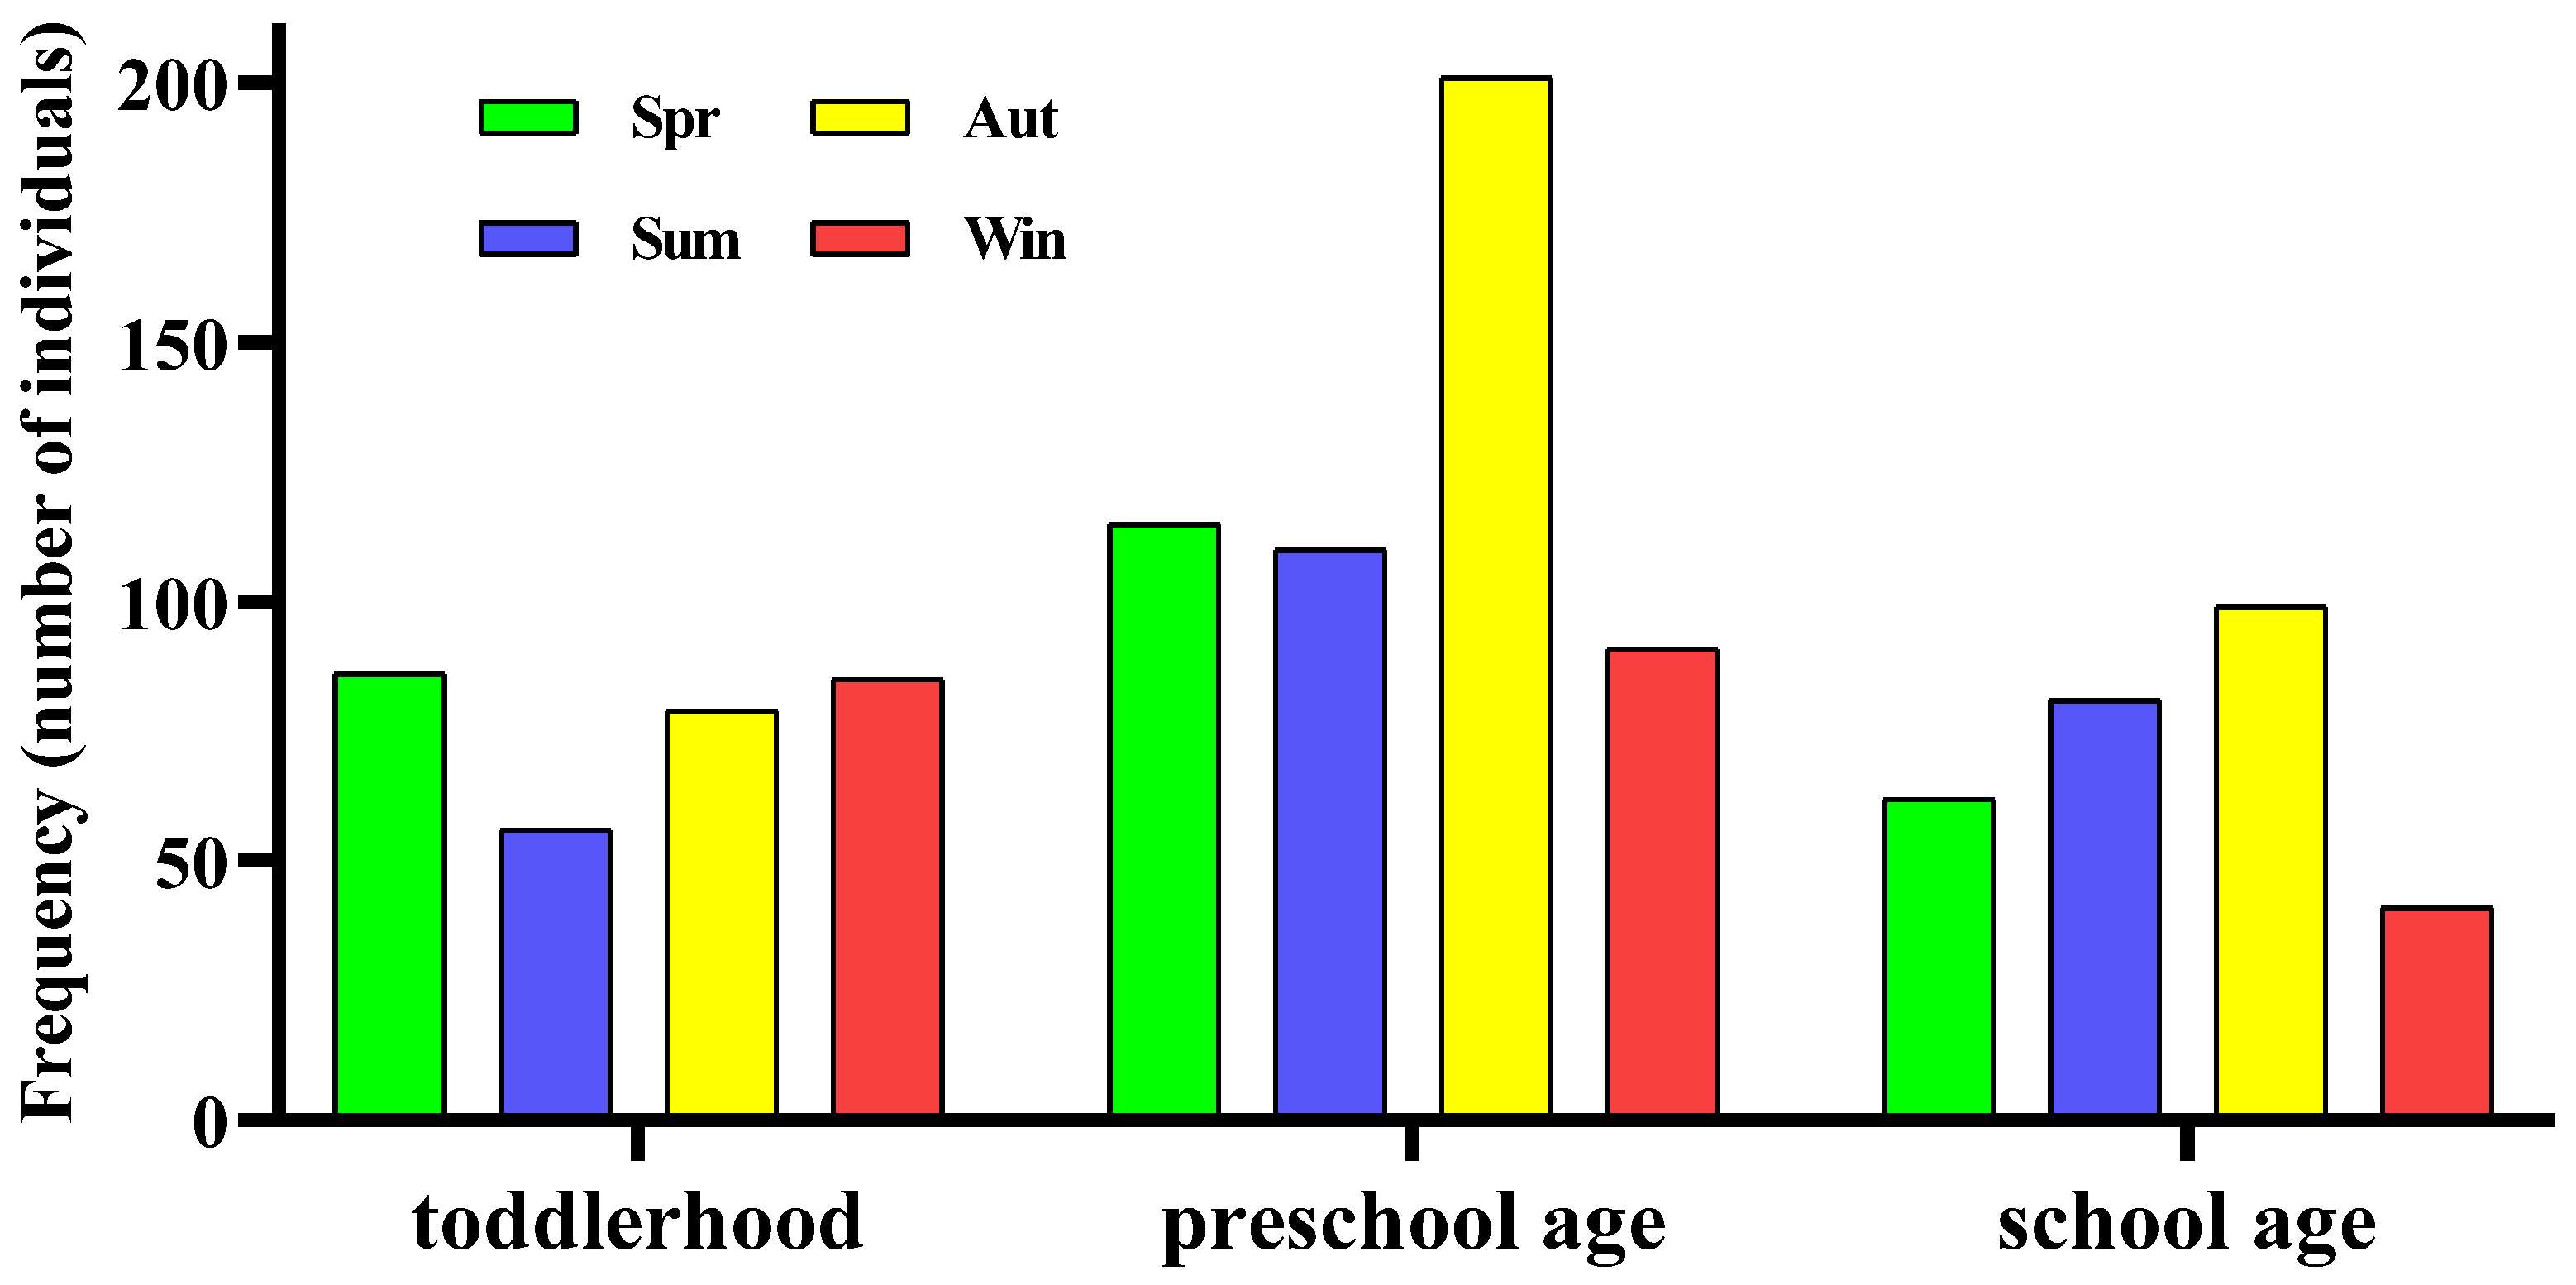
The seasonal distribution of hospitalized children with acute asthma exacerbation varied across age groups. Preschool and school-aged children consistently demonstrated an autumn peak in admissions, as illustrated in Figure 5, whereas toddlerhood children demonstrated a higher admission volume in spring and winter.
Figure 5.
Seasonal distribution of hospitalized children with acute asthma exacerbation across different age groups.
3.8. Gender Differences in Seasonal Distribution
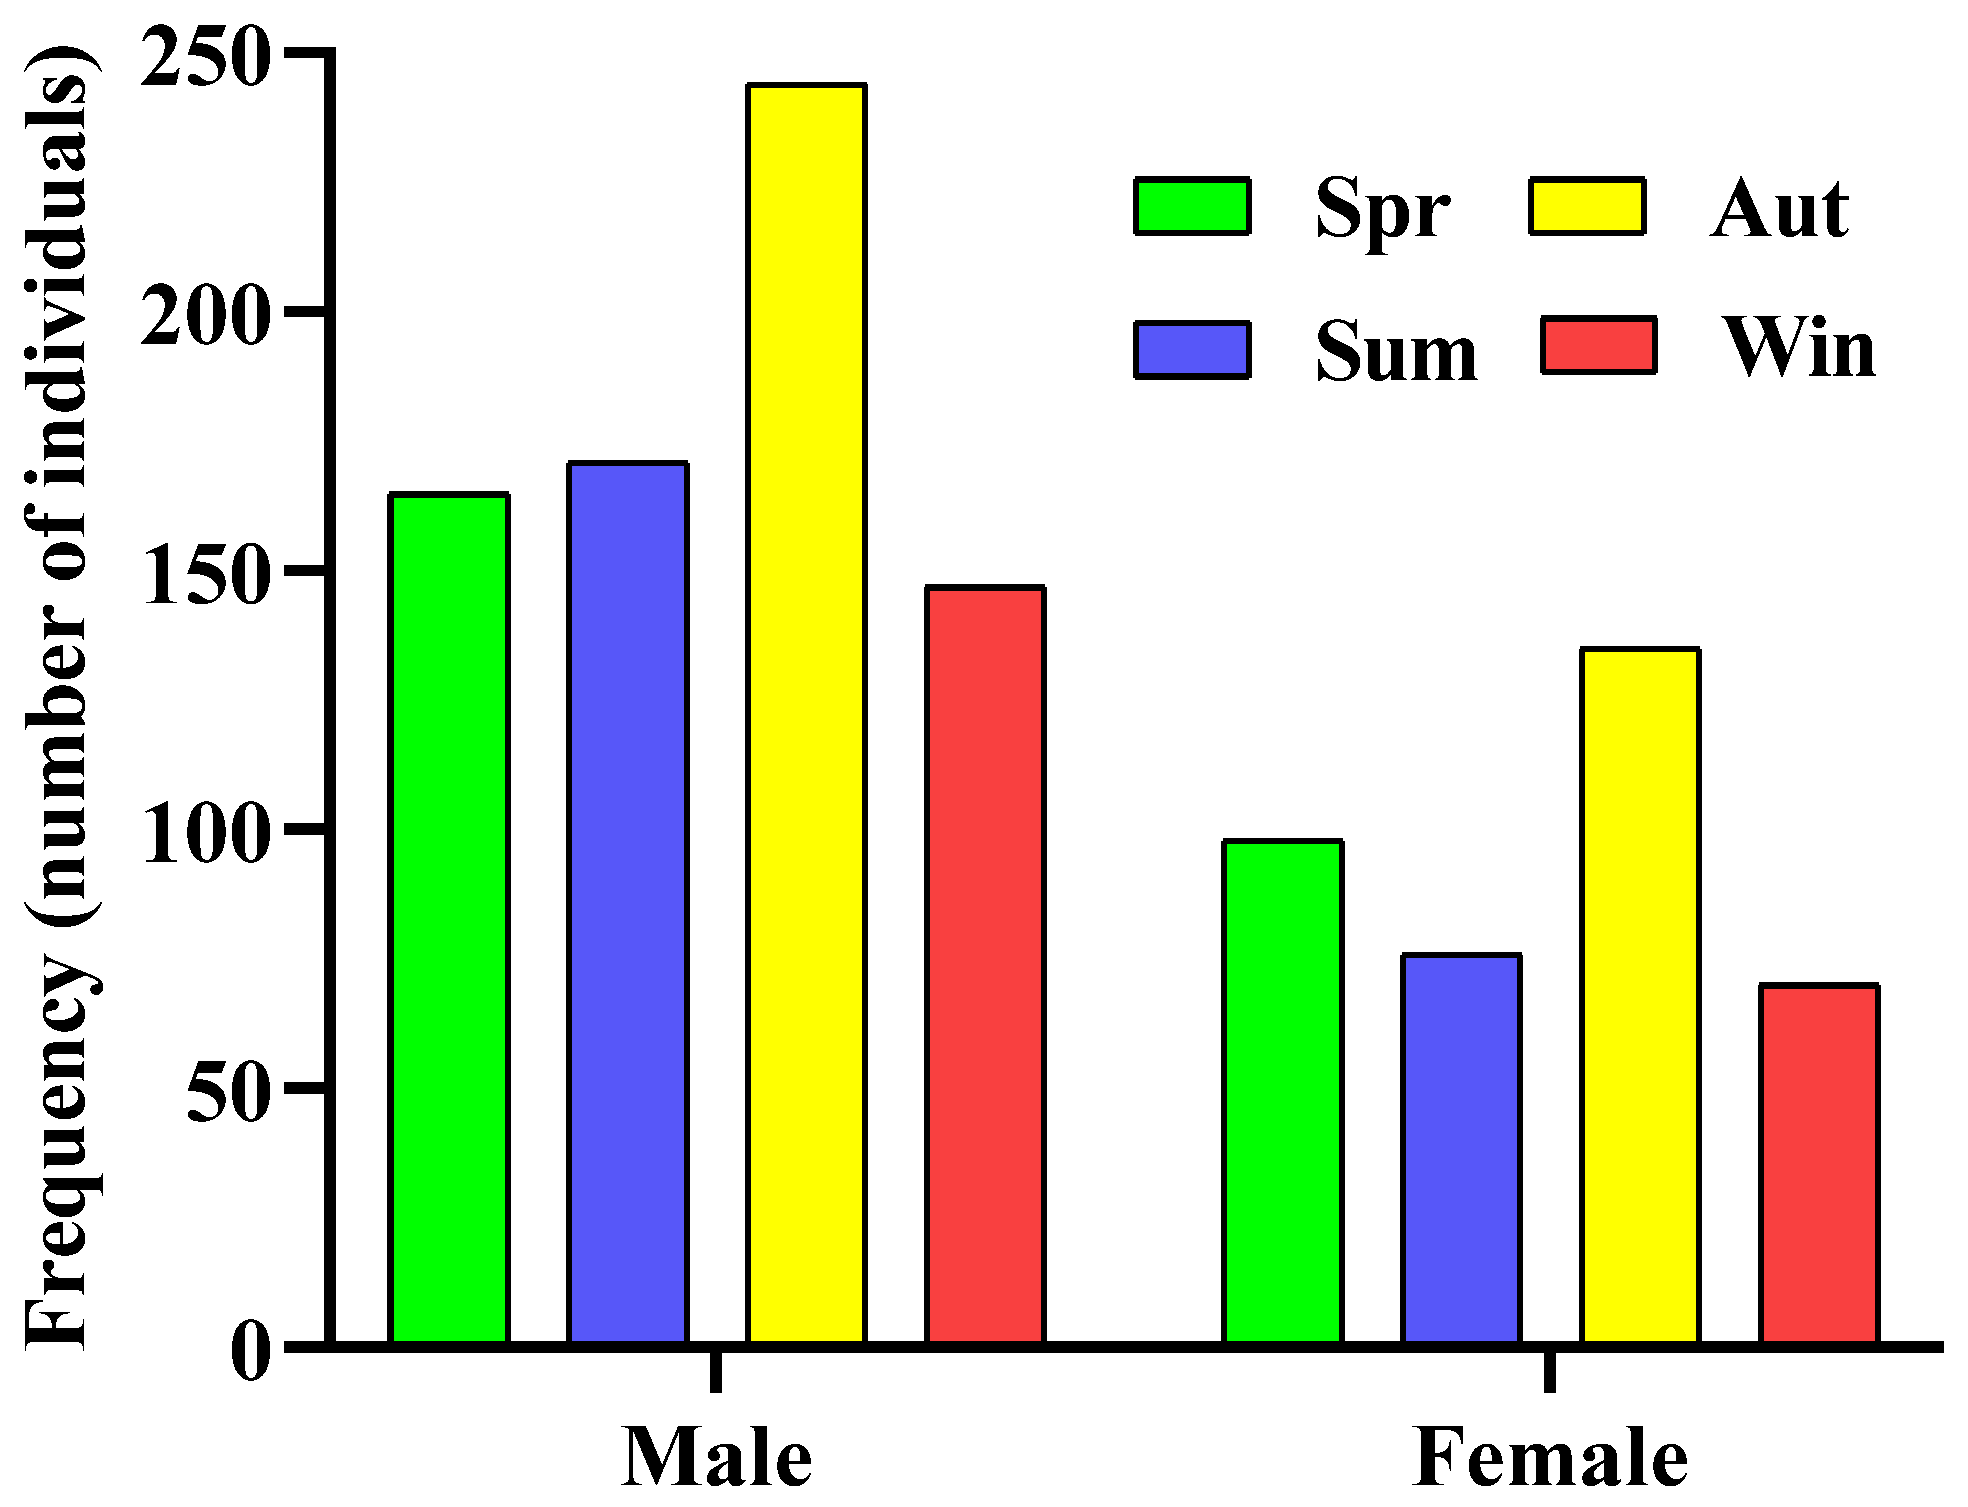
Both genders demonstrated an autumn peak in the seasonal distribution of hospitalized cases, as depicted in Figure 6.
Figure 6.
Seasonal distribution of hospitalized children with acute asthma exacerbation by gender.
3.9. Length of Hospital Stay in Children with Acute Asthma Exacerbation
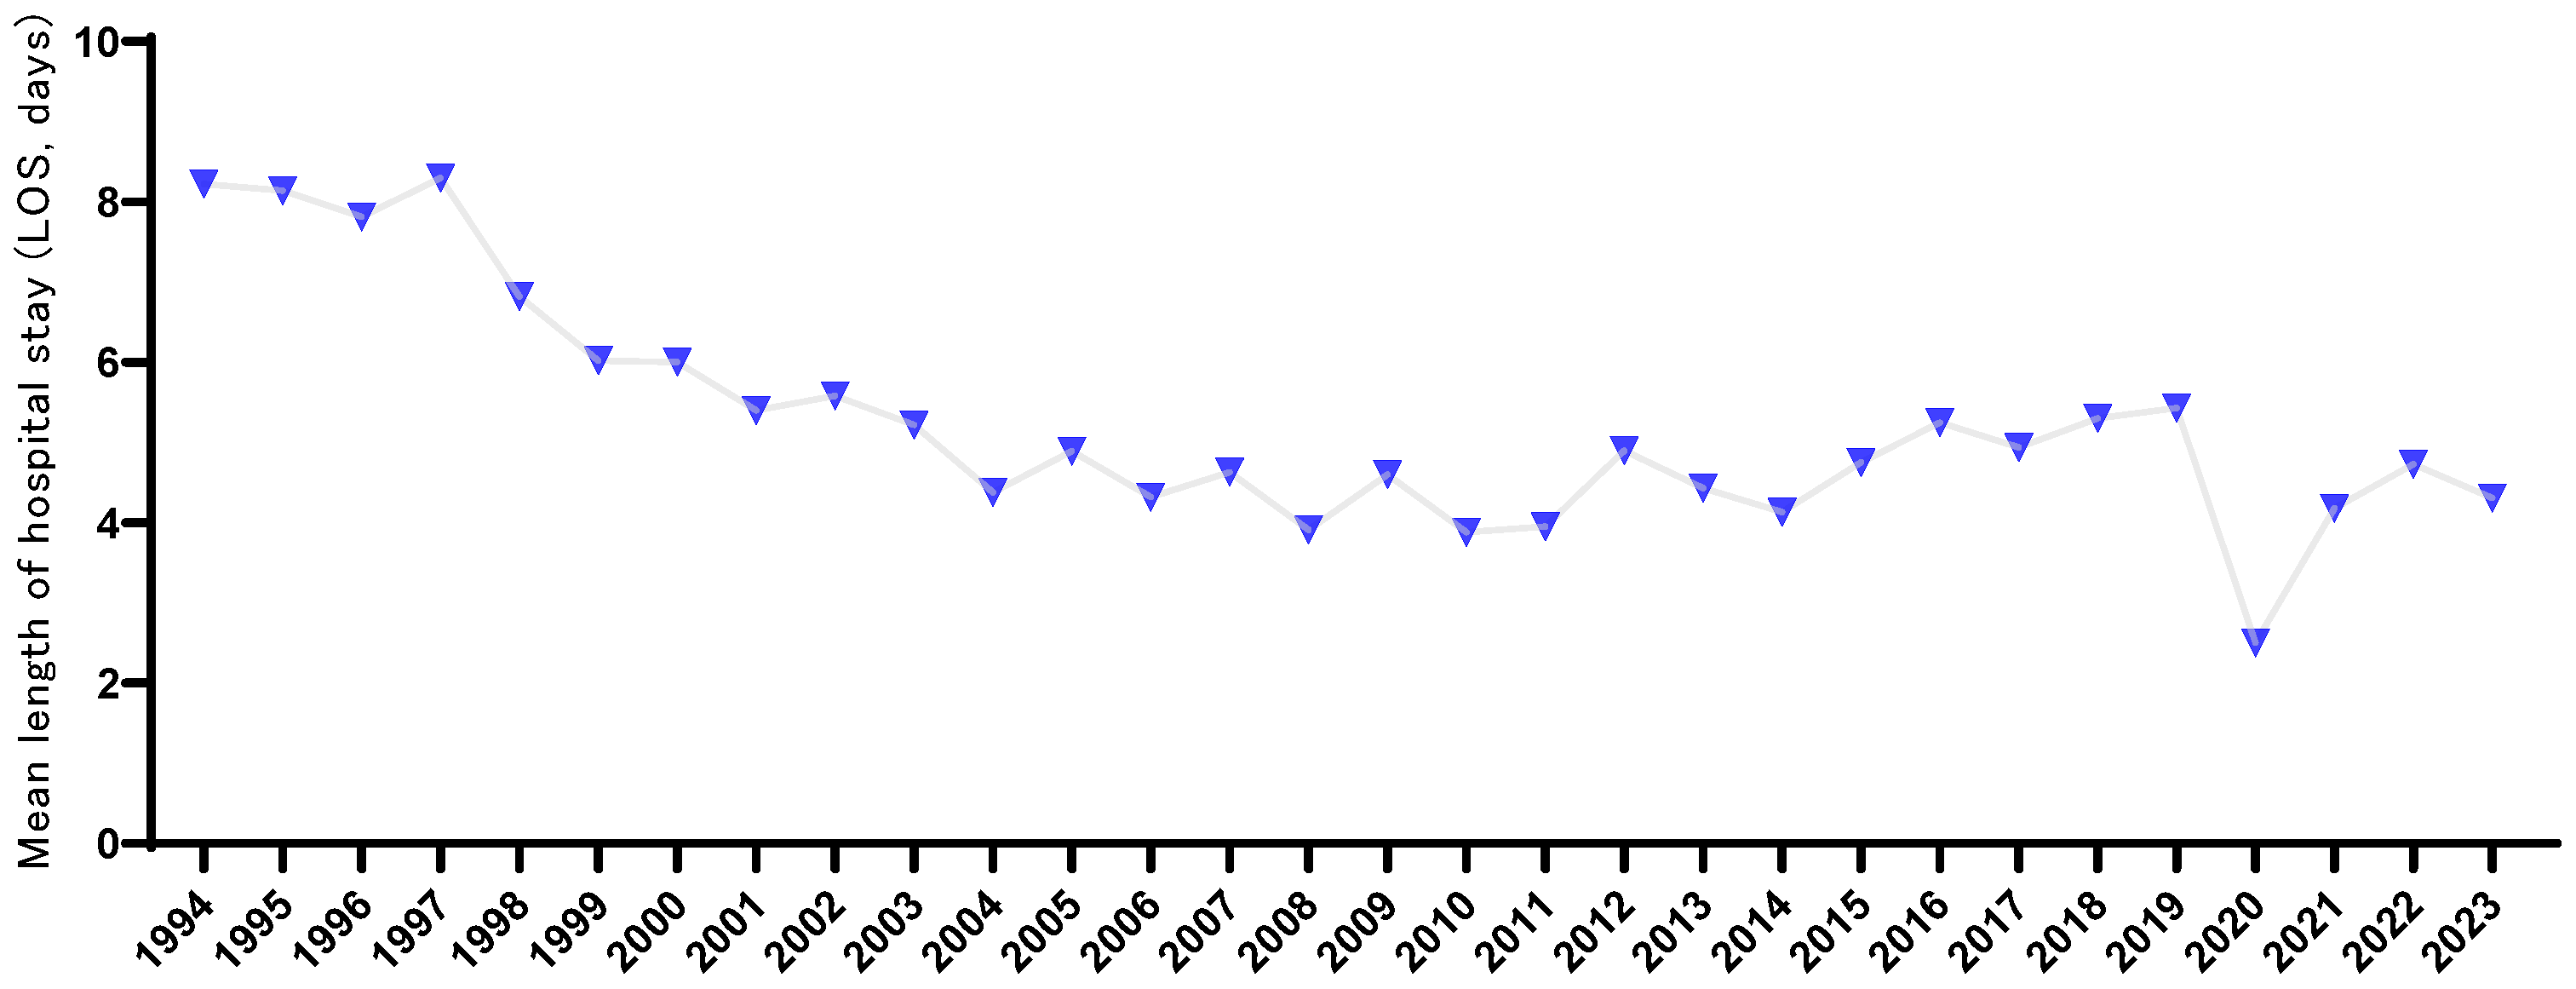
The mean length of hospital stay (LOS) for children admitted with acute asthma exacerbation was 5.35 ± 2.65 days over the 30 years from 1994 to 2023. The overall trend showed a downward decline, followed by a stable plateau from 2004 onward, with the lowest LOS documented in 2020 (Figure 7).
Figure 7.
Annual distribution of mean Length of Hospital Stay (LOS) for acute asthma exacerbation.
3.10. Length of Hospital Stay (LOS) for Acute Asthma Exacerbation Across Different Age Groups
There was a statistically significant difference in LOS among hospitalized children with acute asthma exacerbation across distinct age groups (F = 5.20, p = 0.006). The toddlers demonstrated the longest duration of hospitalization. Post hoc pairwise comparisons (LSD) showed that toddlers had a significantly longer LOS than both preschool children (MD = 0.60 days, 95% CI: 0.22 to 0.97, p = 0.002) and school-age children (mean difference = 0.52 days, 95% CI: 0.09 to 0.95, p = 0.018). In contrast, there was no statistically significant difference in LOS between preschool and school-age children (mean difference = −0.08 days, 95% CI: −0.46 to 0.31, p = 0.689). These results are illustrated in Figure 8.
Figure 8.
Differences in the Length of Hospital Stay (LOS) among hospitalized children with acute asthma exacerbation across age groups. ** p < 0.05.
3.11. Length of Hospital Stay (LOS) for Acute Asthma Exacerbation by Gender
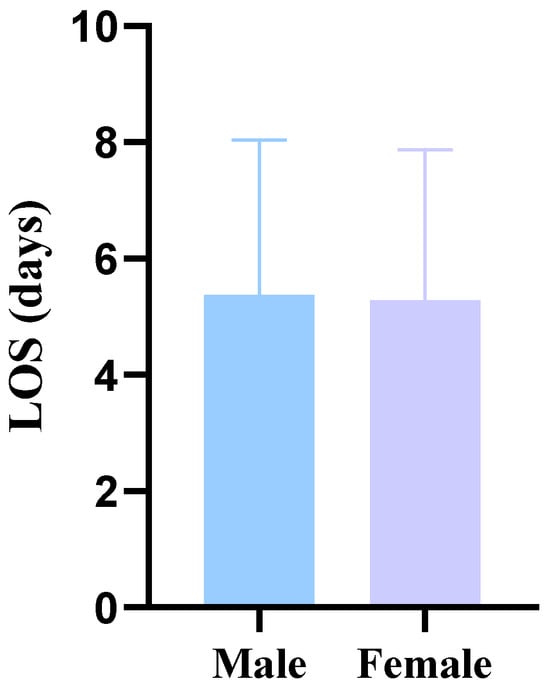
There was no statistically significant difference in LOS between males and females among hospitalized children with acute asthma exacerbation (males: 5.38 ± 2.66 days; females: 5.29 ± 2.58 days; F = 0.95, p = 0.58) (Figure 9).
Figure 9.
Differences in Length of Hospital Stay (LOS) among hospitalized children with acute asthma exacerbation by gender.
4. Discussion
Acute asthma exacerbations are a common cause of pediatric hospitalization [11], yet their long-term epidemiological patterns remain incompletely characterized. In this 30-year (1994–2023) retrospective analysis of clinical data from a tertiary hospital in Beijing, we identified age-specific seasonal patterns of pediatric hospitalizations for acute asthma exacerbations: preschool and school-aged children exhibited an autumn peak, whereas toddlers showed a predominance of exacerbations in spring and winter. This finding suggests that the dominant triggers of asthma exacerbations may differ across age groups—post-enrollment cross-infections may be a key driver in school-aged children, while respiratory viral infections may play a larger role in toddlers. To our knowledge, this is the first 30-year retrospective analysis of pediatric hospitalization trends for acute asthma exacerbations specifically in Beijing, providing long-term epidemiological evidence for this megacity with distinct seasonal air pollution patterns. The sample size of this study was relatively modest; nevertheless, the 30-year follow-up provides valuable longitudinal data for revealing these seasonal and age-specific patterns.
This study found that male children represented a higher proportion of hospitalizations than females, with a male-to-female ratio of approximately 1.9:1, supporting results from earlier studies [12]. This male predominance is consistent with the overall incidence pattern of childhood asthma, where boys are persistently more frequently affected than girls [13]. Notably, this gender disparity gradually narrowed with age: the male-to-female ratios were approximately 2.5:1, 1.8:1, and 1.6:1 in toddlers, preschoolers, and school-aged children, respectively. This pattern aligns with the observed reversal of gender distribution in asthma epidemiology—asthma is more prevalent in young boys, whereas adult women exhibit a higher prevalence—suggesting that hormonal factors may play a role [14,15].
Asthma can occur throughout life but is especially common in childhood. Epidemiological studies show that 87.6% of children with asthma experience their first acute exacerbation by age 5 years [16]. This study revealed that the average age of children hospitalized for acute asthma exacerbations was 4 years. Preschool children represented the largest proportion (46.75%), followed by toddlers (27.67%), which is in accordance with the evidence reported in existing literature [17]. In China, kindergarten enrollment typically begins at age 3. Upon entering kindergarten, children may struggle to adjust to the new environment and are at higher risk for cross-infections—respiratory tract infections are widely recognized as a key precipitating factor for asthma exacerbations. Importantly, the clinical manifestations of asthma in young children are often non-specific. Moreover, many children with wheezing before 3 years discontinue wheezing episodes after 6 years, leading to the consensus that bronchial asthma should not be diagnosed prematurely in this young population [18]. However, our finding of higher hospitalization rates in younger children underscores the urgent need for early accurate diagnosis and timely intervention to prevent exacerbations and optimize long-term clinical outcomes.
The age-specific seasonal pattern was further reflected in monthly admission data. In this 30-year retrospective analysis of a tertiary hospital in Beijing, pediatric asthma admissions peaked in October (147 cases, 13.29%), followed by November (126 cases, 11.39%) and September (106 cases, 9.6%), with the lowest rate in February (45 cases, 4.1%). Multiple biological and environmental factors may contribute to the autumn peak, including elevated ambient pollen concentrations [19], increased proliferation of respiratory pathogens [20], and seasonal fluctuation of indoor dust mite density reaching its annual maximum [21]. As the capital of China with high vehicle ownership, Beijing experiences significantly elevated traffic-related air pollution (TRAP) during the heating season under unfavorable meteorological dispersion conditions, which may synergize with biological factors. Recent studies have revealed that NO2 and PM2.5 damage airway epithelium through oxidative stress-mediated TRPV1 pathway activation, while large diurnal temperature variations and humidity fluctuations in autumn further amplify this effect; concurrently, PM2.5 co-exposure with temperature fluctuations disrupts epithelial barrier function [22,23,24]. Epidemiological studies have also confirmed that the synchronous correlation between autumn PM10 and asthma exacerbations is significantly stronger than in other seasons [25]. These mechanisms corroborate our clinical observations: the October admission peak coincides with the superposition of heating season onset, pollen exposure, pathogen proliferation, and increased cross-infections following school enrollment, creating a multi-hit scenario. While the 2020 decline coincided with the COVID-19 pandemic, this likely reflects both reduced viral transmission from public health measures and altered healthcare-seeking behavior. A study from Chengdu similarly reported a significant drop in monthly asthma cases in February 2020, with higher rates of severe attacks (9.69%) and reduced pulmonary function testing (34.5%), suggesting that milder cases may have avoided hospital care while more severe cases still presented [26]. Additionally, research on rhinovirus (RV) transmission demonstrated that social distancing and school closures markedly reduced respiratory viral infections and asthma healthcare utilization, though RV resurged specifically after school reopening due to its unique resistance to masking and disinfectants. These findings collectively suggest that socially driven factors, including viral transmission dynamics and school policies, played a pivotal role in shaping pediatric asthma hospitalization patterns during the pandemic [27].
The age-specific seasonal pattern we observed suggests that the dominant triggers of asthma exacerbations may differ across age groups. The autumn peak in school-aged and preschool children is consistent with the hypothesis of increased cross-infections following school enrollment. The spring/winter peak in toddlers, by contrast, aligns with the typical seasonality of viral respiratory infections (e.g., RSV, influenza). Although this study lacks direct viral infection data to confirm this mechanism, the age-specific seasonal pattern provides indirect but compelling evidence for trigger-specific hypotheses. Notably, southern regions such as Shanghai, with their subtropical climate and higher humidity, may exhibit distinct seasonal distributions of asthma exacerbations [28]. Therefore, our single-center findings from Beijing may not represent national trends, and multi-center studies across diverse climatic zones in China are needed to understand regional variations. Understanding these marked seasonal variations is essential for enhancing asthma prevention and control strategies. Our findings suggest age-specific targeted preventive measures: for preschool and school-aged children, interventions (e.g., influenza vaccination, reinforcement of asthma action plans) should be implemented before August each year (prior to school reopening); for toddlers, preventive efforts should focus on the winter viral season (e.g., RSV prophylaxis, hand hygiene campaigns). These age-specific, season-specific strategies may inform asthma control policies in Beijing and climatically similar regions, pending validation through future studies with trigger-specific data.
This study was limited by the sole analysis of hospitalization data for acute asthma exacerbations in children, with single-center data that may not reflect national trends or primary/secondary care settings. On the other hand, due to the 30-year retrospective design, complete clinical information was unavailable. Future studies should expand the collection of data to include the incidence of childhood asthma, specific triggers of acute exacerbation episodes, age at the initial onset, treatment modalities, and clinical outcomes, and should incorporate multicenter designs across diverse regions to validate these findings. Such comprehensive analyses will offer more robust data support for the prevention and management of acute asthma exacerbations in children.
5. Conclusions
In conclusion, male patients outnumbered female patients among children aged 1–15 years hospitalized for acute asthma exacerbations in this tertiary center. Preschool children comprised the largest proportion of admissions, with the highest hospitalization rate occurring in autumn and a distinct peak in October. Comprehensive prevention and control strategies should be customized to reduce the incidence and hospitalization rate of childhood acute asthma exacerbations, based on the environmental characteristics of Beijing.
Author Contributions
Conceptualization, X.Z. (Xuee Zhuang) and Y.X. (Yan Xing); methodology, X.Z. (Xuee Zhuang); software, M.L.; validation, K.L., Y.X. (Yangxin Xiao); formal analysis, M.L.; investigation, Y.X. (Yangxin Xiao); resources, Y.X. (Yan Xing); data curation, K.L., X.Z. (Xuyan Zhao); writing—original draft preparation, X.Z. (Xuee Zhuang); writing—review and editing, Y.X. (Yan Xing); visualization, Z.G.; supervision, Y.X. (Yan Xing); project administration, Y.X. (Yan Xing); funding acquisition, Y.X. (Yan Xing). All authors have read and agreed to the published version of the manuscript.
Funding
This research was supported by the Innovation and Translation Fund of Peking University Third Hospital (BYSYZHKC126) and the National Science and Technology Major Project (2025ZD0548700).
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Medical Ethics Committee of Peking University Third Hospital (protocol code M20250542, 31 July 2025). Ethics Approval Number: M20250542.
Informed Consent Statement
Patient consent was waived. Because this article is a retrospective study, the involvement of data from the past 30 years, and it is difficult to obtain the signature of informed consent.
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding authors.
Acknowledgments
Thanks to all the staff and patients and their families who participated in this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| LOS | Length of Hospital Stay |
| ANOVA | One-way analysis of variance |
| IQR | Interquartile range |
| MD | Mean Difference |
| TRAP | Traffic-Related Air Pollution |
| NO2 | Nitrogen Dioxide |
| PM2.5 | Particulate Matter ≤ 2.5 micrometers |
| TRPV1 | Transient Receptor Potential Vanilloid 1 |
| RV | rhinovirus |
References
- Stern, J.; Pier, J.; Litonjua, A.A. Asthma epidemiology and risk factors. Semin. Immunopathol. 2020, 42, 5–15. [Google Scholar] [CrossRef] [Scilit]
- Zhou, W.; Tang, J. Prevalence and risk factors for childhood asthma: A systematic review and meta-analysis. BMC Pediatr. 2025, 25, 50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shin, Y.H.; Hwang, J.; Kwon, R.; Lee, S.W.; Kim, M.S.; Shin, J.I.; Yon, D.K. Global, regional, and national burden of allergic disorders and their risk factors in 204 countries and territories, from 1990 to 2019: A systematic analysis for the Global Burden of Disease Study 2019. Allergy 2023, 78, 2232–2254. [Google Scholar] [CrossRef] [Scilit]
- Wang, J.; Zhou, Y.; Zhang, H.; Hu, L.; Liu, J.; Wang, L.; Wang, T.; Zhang, H.; Cong, L.; Wang, Q. Pathogenesis of allergic diseases and implications for therapeutic interventions. Signal Transduct. Target. Ther. 2023, 8, 138. [Google Scholar] [CrossRef] [Scilit]
- Ducharme, F.M.; Zemek, R.; Chauhan, B.F.; Gravel, J.; Chalut, D.; Poonai, N.; Guertin, M.C.; Quach, C.; Blondeau, L.; Laberge, S. Factors associated with failure of emergency department management in children with acute moderate or severe asthma: A prospective, multicentre, cohort study. Lancet Respir. Med. 2016, 4, 990–998. [Google Scholar] [CrossRef] [Scilit]
- National Cooperative Group on Childhood Asthma Control. Standard procedures for diagnosis and treatment of childhood asthma (trial version). Chin. J. Tuberc. Respir. Dis. 1993, 16, 10–12. [Google Scholar] [CrossRef]
- National Cooperative Group on Childhood Asthma Control. Standardized procedures for childhood asthma prevention and treatment (trial version). Chin. J. Pediatr. 1998, 36, 747–751. [Google Scholar] [CrossRef]
- Subspecialty Group of Respiratory Diseases, Society of Pediatrics; Chinese Medical Association; Editorial Board of Chinese Journal of Pediatrics. The routine for prevention and treatment of bronchial asthma in children (for trial). Chin. J. Pediatr. 2004, 42, 100–106. [Google Scholar] [CrossRef]
- Subspecialty Group of Respiratory Diseases, Society of Pediatrics; Chinese Medical Association; Editorial Board of Chinese Journal of Pediatrics. Guideline for the diagnosis and optimal management of asthma in children. Chin. J. Pediatr. 2008, 46, 745–753. [Google Scholar] [CrossRef]
- Subspecialty Group of Respiratory Diseases, Society of Pediatrics; Chinese Medical Association; Editorial Board of Chinese Journal of Pediatrics. Guideline for the diagnosis and optimal management of asthma in children (2016). Chin. J. Pediatr. 2016, 54, 167–181. [Google Scholar] [CrossRef] [Scilit]
- Pijnenburg, M.W.; Fleming, L. Advances in understanding and reducing the burden of severe asthma in children. Lancet Respir. Med. 2020, 8, 1032–1044. [Google Scholar] [CrossRef] [Scilit]
- Cheng, J.; Tsang, Y.P.; Lam, Y.Y.; Chu, A.K.Y.; Ng, C.S.Y.; Chan, C.H.Y.; Fung, Y.L.; Chau, P.S.Y.; Luk, D.C.K. Prevalence and severity of asthma among school children in Hong Kong. Hong Kong Med. J. 2024, 30, 371–379. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.; Shi, H.; Wan, G.; Zhao, Z.; Norback, D.; Pu, G.; Ma, S.; Dong, H.; Yao, J.; Lu, J.; et al. Prevalence and influencing factors of wheeze and asthma among preschool children in Urumqi city: A cross-sectional survey. Sci. Rep. 2023, 13, 2263. [Google Scholar] [CrossRef] [Scilit]
- Chowdhury, N.U.; Guntur, V.P.; Newcomb, D.C.; Wechsler, M.E. Sex and gender in asthma. Eur. Respir. Rev. 2021, 30, 210067. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosas-Salazar, C.; Chirkova, T.; Gebretsadik, T.; Chappell, J.D.; Peebles, R.S., Jr.; Dupont, W.D.; Jadhao, S.J.; Gergen, P.J.; Anderson, L.J.; Hartert, T.V. Respiratory syncytial virus infection during infancy and asthma during childhood in the USA (INSPIRE): A population-based, prospective birth cohort study. Lancet 2023, 401, 1669–1680. [Google Scholar] [CrossRef] [Scilit]
- Moral, L.; Vizmanos, G.; Torres-Borrego, J.; Praena-Crespo, M.; Tortajada-Girbés, M.; Pellegrini, F.J.; Asensio, Ó. Asthma diagnosis in infants and preschool children: A systematic review of clinical guidelines. Allergol. Immunopathol. 2019, 47, 107–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jackson, D.J.; Gern, J.E. Rhinovirus infections and their roles in asthma: Etiology and exacerbations. J. Allergy Clin. Immunol. Pract. 2022, 10, 673–681. [Google Scholar] [CrossRef] [Scilit]
- Bacharier, L.B.; Guilbert, T.W.; Jartti, T.; Saglani, S. Which wheezing preschoolers should be treated for asthma? J. Allergy Clin. Immunol. Pract. 2021, 9, 2611–2618. [Google Scholar] [CrossRef] [Scilit]
- Lappe, B.L.; Ebelt, S.; D’Souza, R.R.; Manangan, A.; Brown, C.; Saha, S.; Harris, D.; Chang, H.H.; Sole, A.; Scovronick, N. Pollen and asthma morbidity in Atlanta: A 26-year time-series study. Environ. Int. 2023, 177, 107998. [Google Scholar] [CrossRef] [Scilit]
- Hu, Y.; Cheng, J.; Jiang, F.; Liu, S.; Li, S.; Tan, J.; Yin, Y.; Tong, S. Season-stratified effects of meteorological factors on childhood asthma in Shanghai, China. Environ. Res. 2020, 191, 110115. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Cui, L.; Hou, J.; Luo, S.; Norbäck, D.; Sundell, J. Role of ventilation and cleaning for controlling house dust mite allergen infestation: A study on associations of house dust mite allergen concentrations with home environment and life styles in Tianjin area, China. Indoor Air 2022, 32, e13084. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, C.; Liu, Q.; Deng, M.; Liao, H.; Yang, X.; Ma, P. Interaction of high temperature and NO2 exposure on asthma risk: In Vivo experimental evidence of inflammation and oxidative stress. Sci. Total Environ. 2023, 869, 161760. [Google Scholar] [CrossRef] [Scilit]
- Lu, C.; Liu, Q.; Qiao, Z.; Yang, X.; Baghani, A.N.; Wang, F. High humidity and NO2 co-exposure exacerbates allergic asthma by increasing oxidative stress, inflammatory and TRP protein expressions in lung tissue. Environ. Pollut. 2024, 353, 124127. [Google Scholar] [CrossRef] [Scilit]
- Lu, C.; Wang, F.; Liu, Q.; Deng, M.; Yang, X.; Ma, P. Effect of NO2 exposure on airway inflammation and oxidative stress in asthmatic mice. J. Hazard. Mater. 2023, 457, 131787. [Google Scholar] [CrossRef] [Scilit]
- Lu, C.; Wang, F.; Qiao, Z.; Deng, M.; Liu, Q.; Yang, X. Extreme temperatures exacerbated oxidative stress and airway inflammation in a mouse model of allergic asthma. Allergy 2024, 79, 1333–1335. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Wang, X.; Huang, Y.; Ai, T.; Liao, H.; Hu, J.; Tang, W.; Huang, Y. Pediatric Asthma Situation in Chengdu, China, During the COVID-19 Pandemic: An Observational Study. J. Asthma Allergy 2021, 14, 829–838. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kreger, J.E.; Hershenson, M.B. Effects of COVID-19 and Social Distancing on Rhinovirus Infections and Asthma Exacerbations. Viruses 2022, 14, 2340. [Google Scholar] [CrossRef] [Scilit]
- Lei, X.; Liu, L.; Chen, R.; Liu, C.; Hong, J.; Cao, L.; Lu, Y.; Dong, X.; Chen, X.; Qiu, X.; et al. Temperature changes between neighboring days and childhood asthma: A seasonal analysis in Shanghai, China. Int. J. Biometeorol. 2021, 65, 827–836. [Google Scholar] [CrossRef] [Scilit] [PubMed]
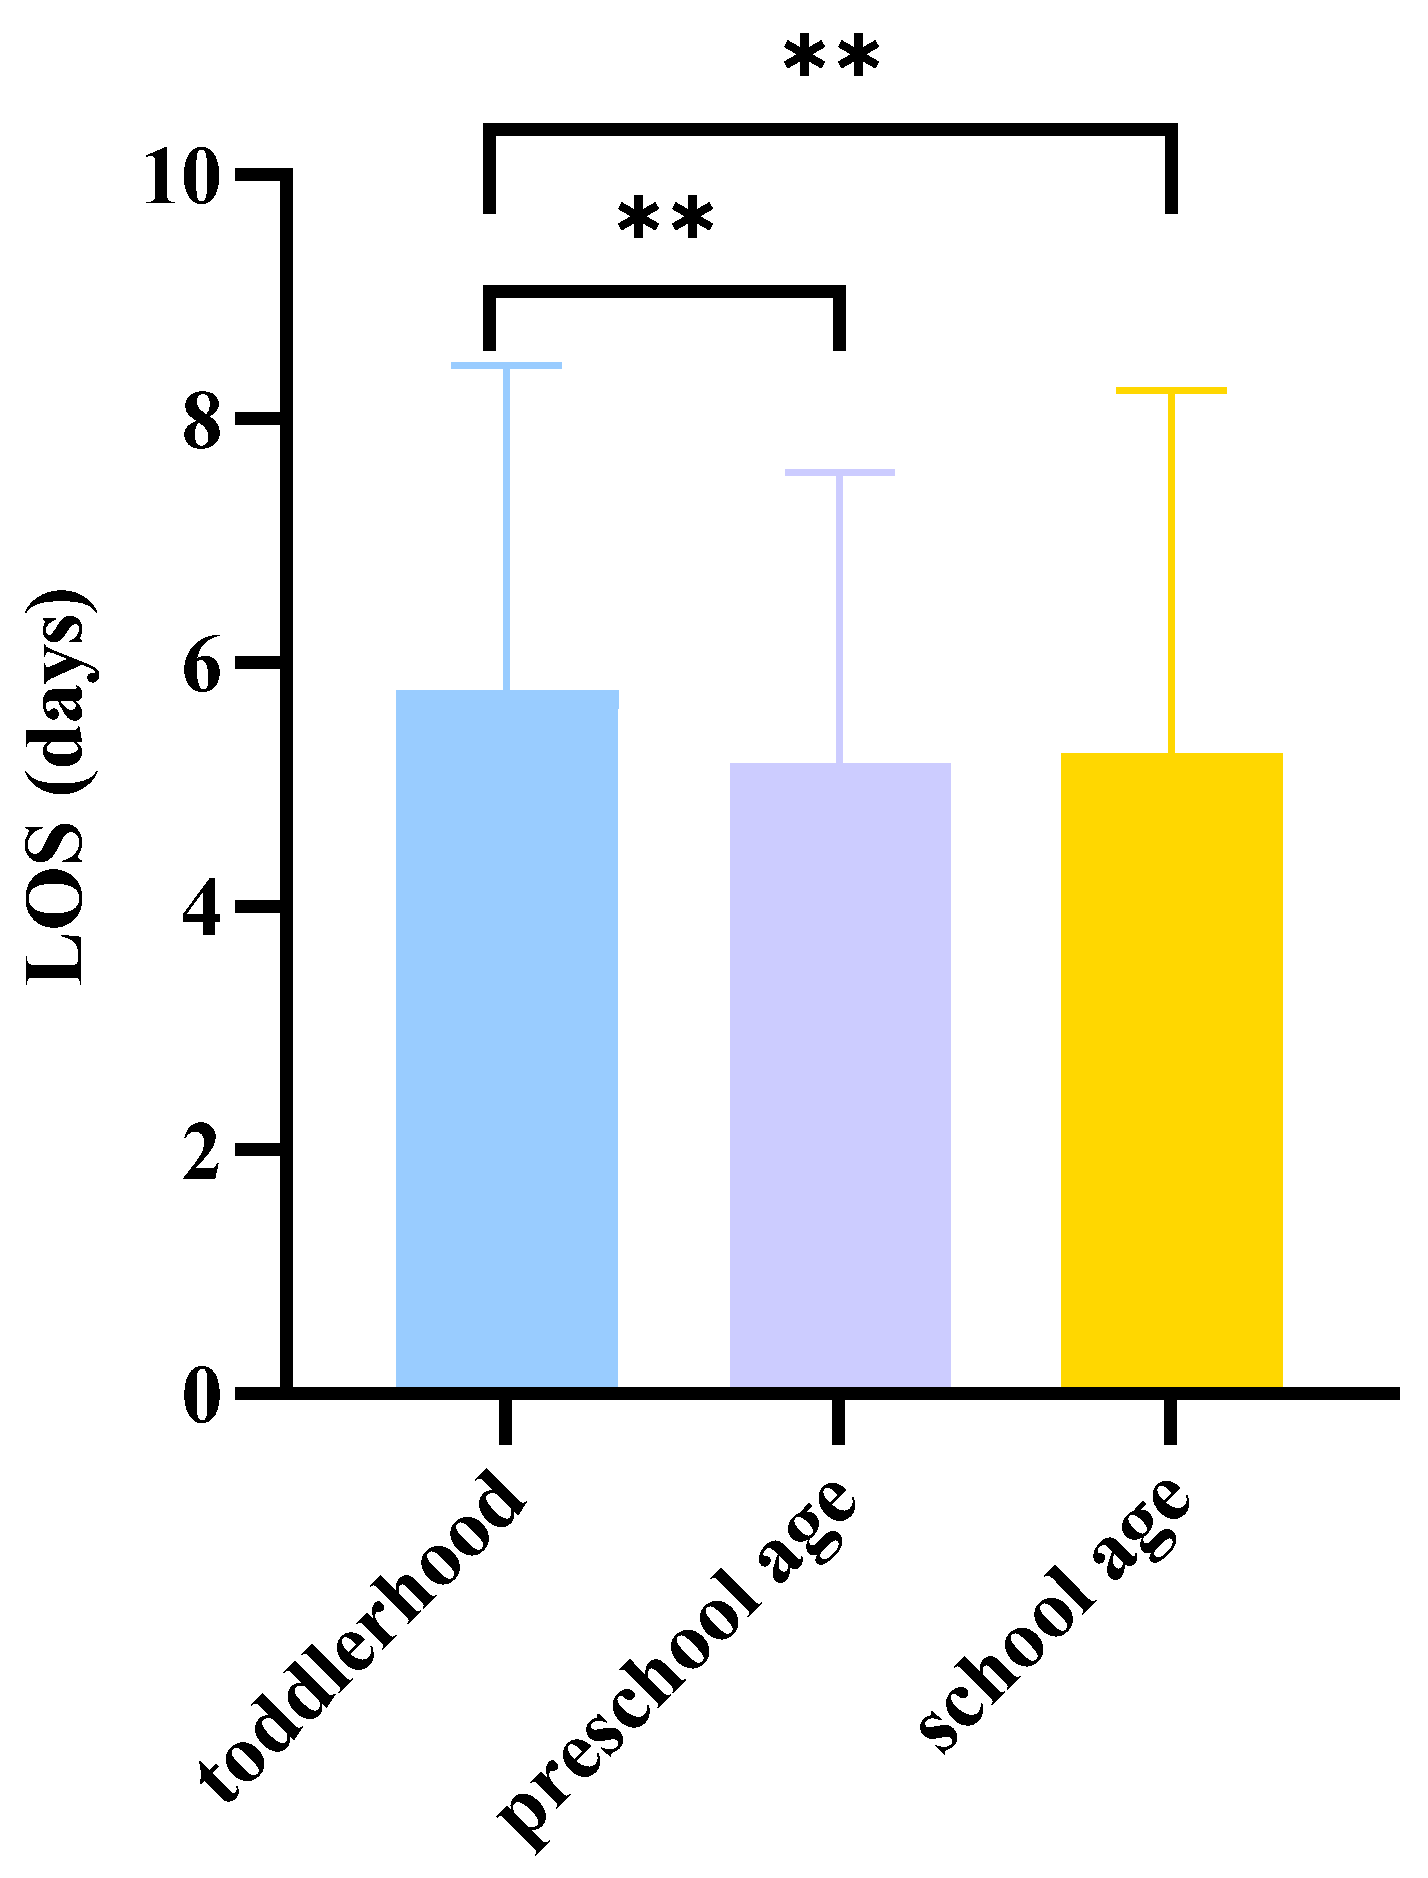

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the Polish Respiratory Society. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.