Article

Effect of Polishing Protocols and Sugar on the Colour Stability and Stain Reversibility of Supra-Nanospherical Resin Composites: An In Vitro Study

by
Hawnaz Wshyar
* and
Gollshang Ahmad Mhammed Dalloo
Conservative Department, College of Dentistry, University of Sulaimani, City Campus—Zanko Street—Sulaimania, Kurdistan Region, Sulaymaniyah 0046, Iraq
*
Author to whom correspondence should be addressed.
J. Compos. Sci. 2026, 10(8), 398; https://doi.org/10.3390/jcs10080398
Submission received: 21 June 2026 / Revised: 24 July 2026 / Accepted: 27 July 2026 / Published: 29 July 2026
(This article belongs to the Section Nanocomposites)

Abstract

Dental composites are ceramic-reinforced polymers; however, their colour stability is crucial for clinical maintenance, as composite restorations are inherently susceptible to colour change over time. In this in vitro study, eighty standardised 3D-printed samples were fabricated, filled with one of two supra-nanospherical resin composites, divided according to two polishing protocols (standard and reduced), and immersed in black tea with or without sugar for 28 days, after which they were repolished. Colour measurements were performed using a spectrophotometer at baseline (T1), after tea immersion (T2), and after repolishing (T3). Statistical analysis was performed using a three-way repeated-measures mixed ANOVA followed by a Bonferroni post hoc test. The colour outcomes were interpreted against the CIEDE2000 50:50% perceptibility threshold (PT00 = 0.8) and acceptability threshold (AT00 = 1.8). Given the constraints of this in vitro investigation, all specimens exhibited initial discolouration (ΔE001 = 5.85 ± 1.63) that exceeded the acceptability threshold. Following repolishing, overall discolouration was significantly reduced (5.64 ± 1.46), achieving a final recovery (ΔE003 of 0.92 ± 0.56) near the perceptibility threshold. Although Tokuyama PALFIQUE® LX5 might have exhibited lower ΔE than Estelite® Alpha, the choice of composite had no statistically significant impact. Conversely, polishing methods and sugar content significantly influenced the outcomes (p < 0.05). Specifically, the standard method consistently resulted in final residual colour differences below the perceptibility threshold (ΔE003 ≤ PT), whereas the reduced method resulted in values exceeding this threshold. Furthermore, exposure to sucrose resulted in significantly greater residual staining post-treatment compared to plain black tea. Within the limitations of this in vitro study, the findings suggest that while composite selection between similar supra-nanospherical resins does not significantly affect aesthetic longevity, the standard method effectively maintains final residual colour shifts within imperceptible clinical boundaries. Moreover, dietary sucrose may contribute to greater permanent residual staining after repolishing. Nonetheless, as these observations derive from an in vitro model lacking a natural salivary pellicle and biofilm, clinical in vivo validation is required before direct extrapolation to daily dental practice.

1. Introduction

The demand for aesthetically pleasing dental restorations has risen significantly in recent decades. This trajectory is propelled by increasing patient expectations for less invasive, aesthetically appealing, and sustainable treatments [1,2,3]. Various clinical procedures can address anterior aesthetic conditions, with both direct and indirect veneers being widely implemented. Direct veneers offer distinct advantages, including minimal tooth preparation, lower costs, and single-visit completion. They also allow convenient intraoral replacement. Nevertheless, these restorations remain highly technique-sensitive, and clinicians frequently struggle to maintain prolonged colour stability and a superior surface finish [4,5].
A major clinical challenge for composite restorations is discolouration, which arises from both intrinsic and extrinsic factors. Intrinsic factors include matrix resin deterioration, water penetration, and filler breakdown. Extrinsic factors involve dietary chromogens found in coffee, tea, and red wine. Inadequate finishing or polishing procedures also contribute to surface staining. Together, these mechanisms enhance stain infiltration, modify colour perception, and ultimately diminish patient satisfaction [6,7,8,9,10].
Laboratory studies require reproducible specimen fabrication to investigate these aesthetic challenges. Computer-aided design and additive manufacturing (CAD/CAM) technologies provide exceptional prospects for this standardisation [11]. Vat-polymerisation systems like stereolithography (SLA) and digital light processing (DLP) are particularly useful, as their resin rheology and post-processing parameters significantly influence clinical precision and wear characteristics [12]. In the present experimental study, three-dimensional printing was specifically utilised to manufacture uniform resin moulds. This ensured consistent specimen geometry and identical baseline surface characteristics across all experimental groups [13].
Nanotechnology is now incorporated into contemporary resin composites to improve aesthetic durability. This includes adding supra-nanospherical fillers into methacrylate-based organic matrices. Typical fillers include zirconium dioxide (ZrO2) and silicon dioxide (SiO2) [14]. Furthermore, adequate polishing contributes significantly to colour stability, gloss retention, and pigmentation resistance [15]. Polishing strategies are generally categorised into standard and reduced methods. The standard method (multi-step protocols) incorporates consecutive abrasive discs from coarse to extra-fine, often followed by polishing paste. The reduced method (two-step protocols) is designed to maximise chairside efficiency without compromising surface quality [16]. Spectrophotometric analysis using the Commission Internationale de l’Eclairage (CIEDE2000) formula serves as the gold standard for quantitatively measuring colour change (ΔE). It allows colour shifts to be rigorously assessed against established perceptibility and acceptability thresholds [17,18,19].
Discolouration caused by common beverages like black tea has been extensively investigated; despite this, the influence of widespread dietary additives like sucrose has received limited attention [9]. This represents a significant knowledge gap despite its obvious clinical relevance. Considering that carbohydrates may lead to surface deterioration and pigment retention, they might exacerbate discolouration when added to the daily beverages [20]. Investigating this dietary co-factor is essential, as it bridges the gap between simplified laboratory immersion models and realistic human dietary habits.
Therefore, the objectives of this experimental in vitro study were to evaluate the colour stability and stain reversibility of supra-nanospherical resin composites exposed to an aqueous tea immersion medium with and without added dietary sugar. Furthermore, we compared the stain removal efficacy of two distinct polishing protocols across sequential time phases. The corresponding null hypotheses were that neither the addition of sugar nor the type of composite resin would significantly affect colour change and that the polishing protocol utilised would not influence stain removal efficacy.
Accordingly, this experimental in vitro study evaluated the colour stability and stain reversibility of supra-nanospherical resin composites. We specifically investigated the influence of adding dietary sugar to an aqueous tea immersion medium. Furthermore, we compared the stain removal efficacy of two distinct polishing protocols across sequential time phases. The corresponding null hypothesis was that neither the addition of sugar nor the type of composite resin would significantly affect overall colour change. Additionally, we hypothesised that the polishing protocol utilised would not influence stain removal efficacy.

2. Materials and Methods

2.1. Sample Preparation and Sample Size

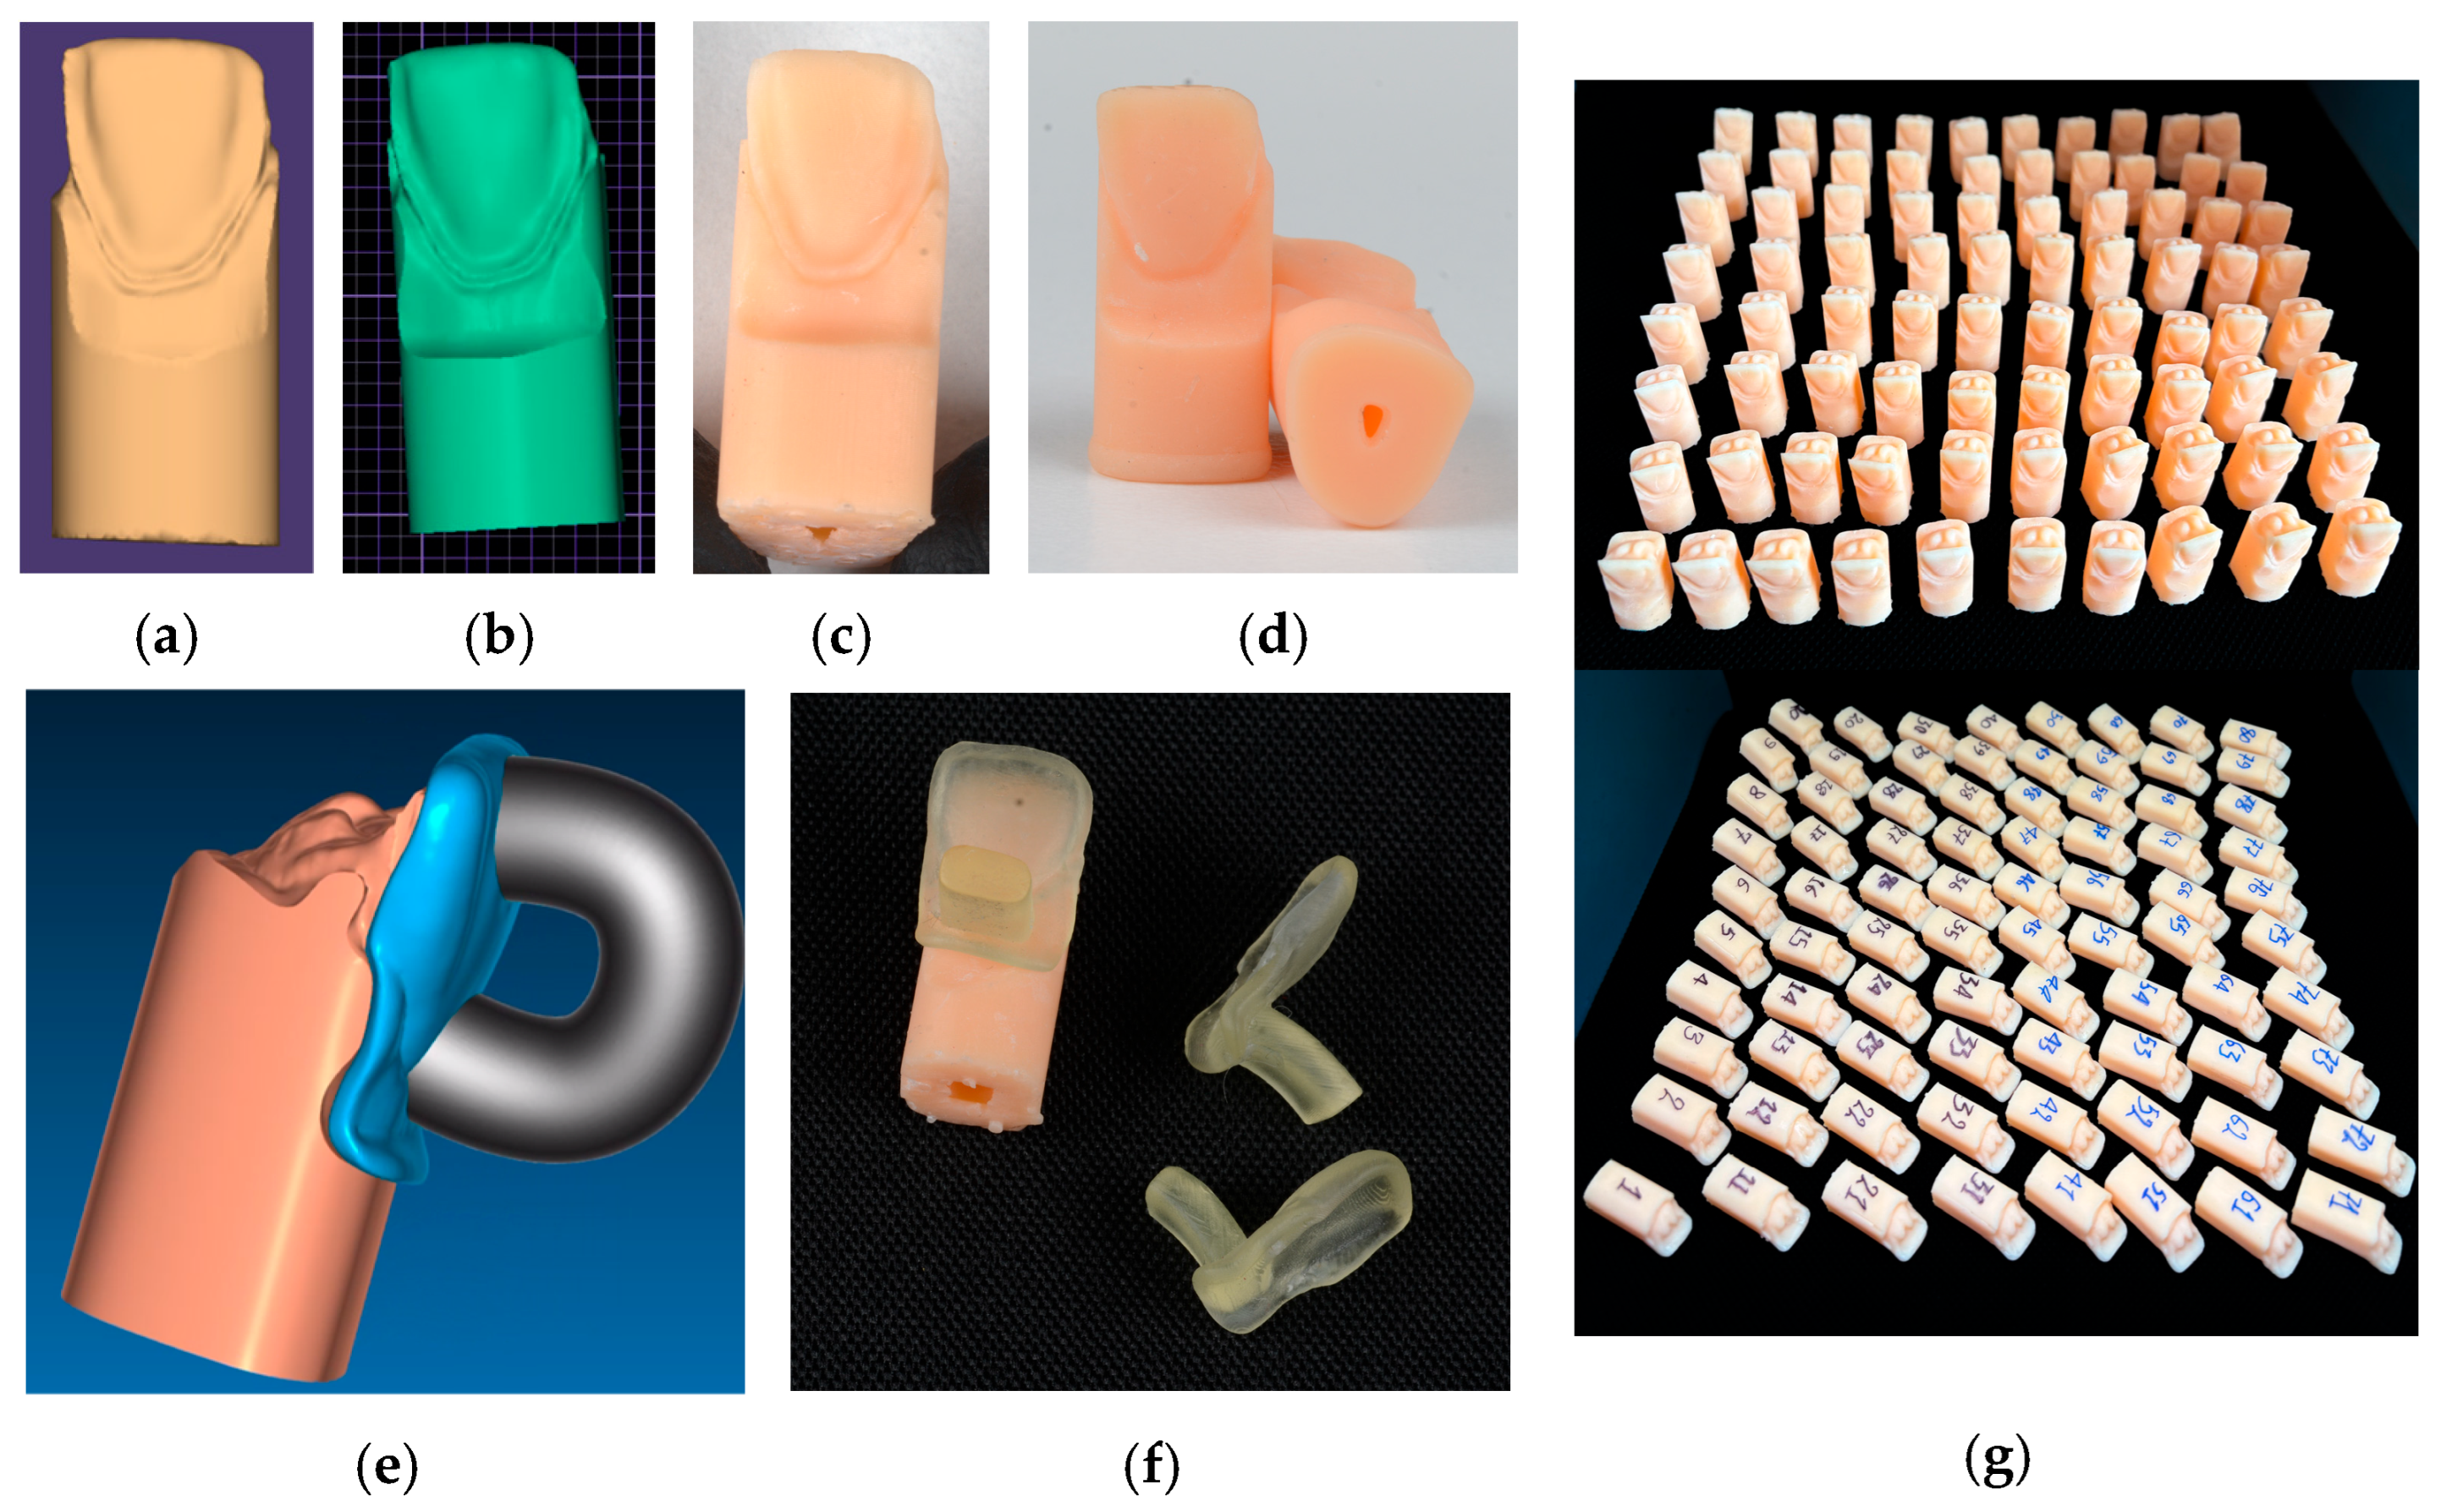
In this in vitro study, 3D-printed samples were chosen instead of flat discs to replicate an actual natural tooth in terms of angulations and dimensions. Consequently, an artificial maxillary right central incisor with measurements mimicking an ideal natural tooth was printed by utilising a DLP 3D printer (SprintRay Pro 2, SprintRay Inc., Los Angeles, CA, USA) to construct a guide over it. To avoid errors during the process, a clear guide was printed with the same device using a clear resin (MAZIC D SG; Vericom Co., Ltd., Chuncheon, Gangwon-do, Republic of Korea). This single-tooth guide was used in a stamp technique during composite filling so that all the samples were standardised with identical anatomical contours. Subsequently, 80 samples of the same tooth prepared for direct veneers were printed using the aforementioned printer and resin material (Dental Model, Dune shade; SprintRay Inc., Los Angeles, CA, USA), ensuring that all samples possessed identical ideal measurements (Figure 1, Table 1).
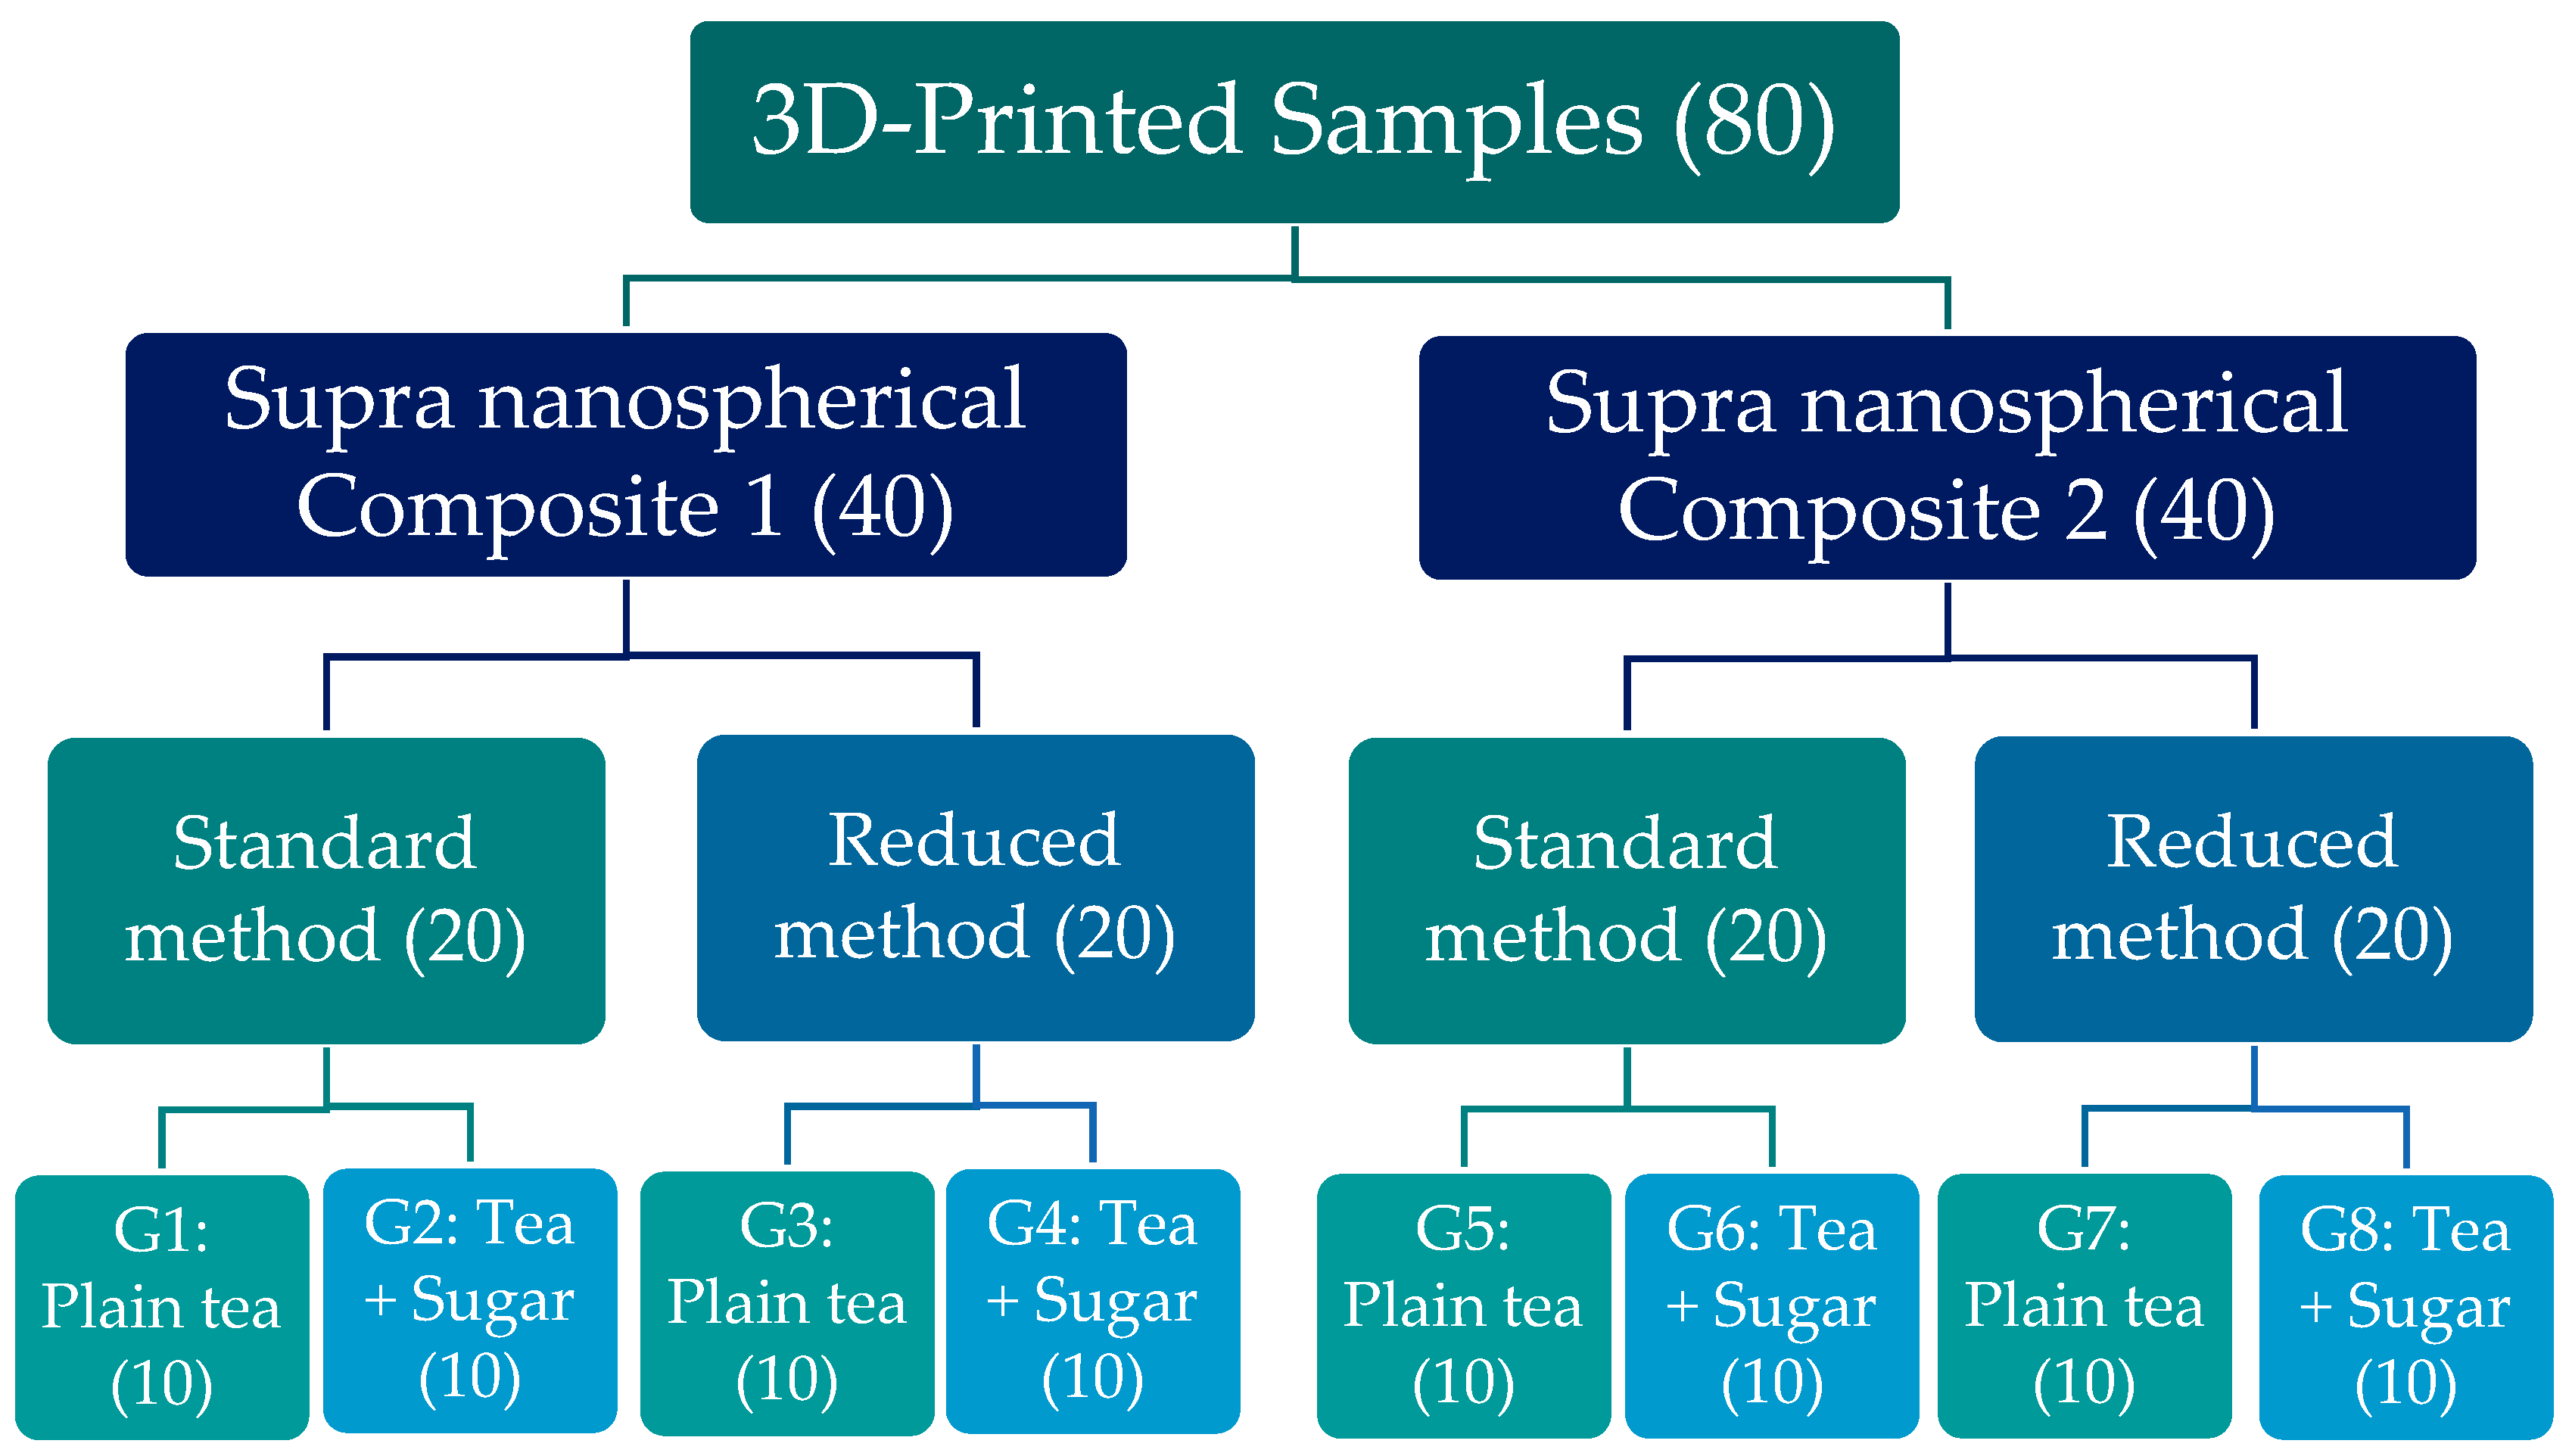
The sample size was determined using statistical software (G*Power version 3.1.9.7, Heinrich-Heine-Universität Düsseldorf, Düsseldorf, Germany) based on effect sizes reported in comparable in vitro colour stability literature. To achieve a statistical power of 95% at a significance level of (α = 0.05) with an expected medium effect size (f = 0.25), a minimum of 10 specimens per experimental group (n = 10) was required. Following fabrication, all specimens were randomly allocated into their respective experimental groups and subsequently numbered, as shown in Scheme 1.

2.2. Direct Composite Protocol

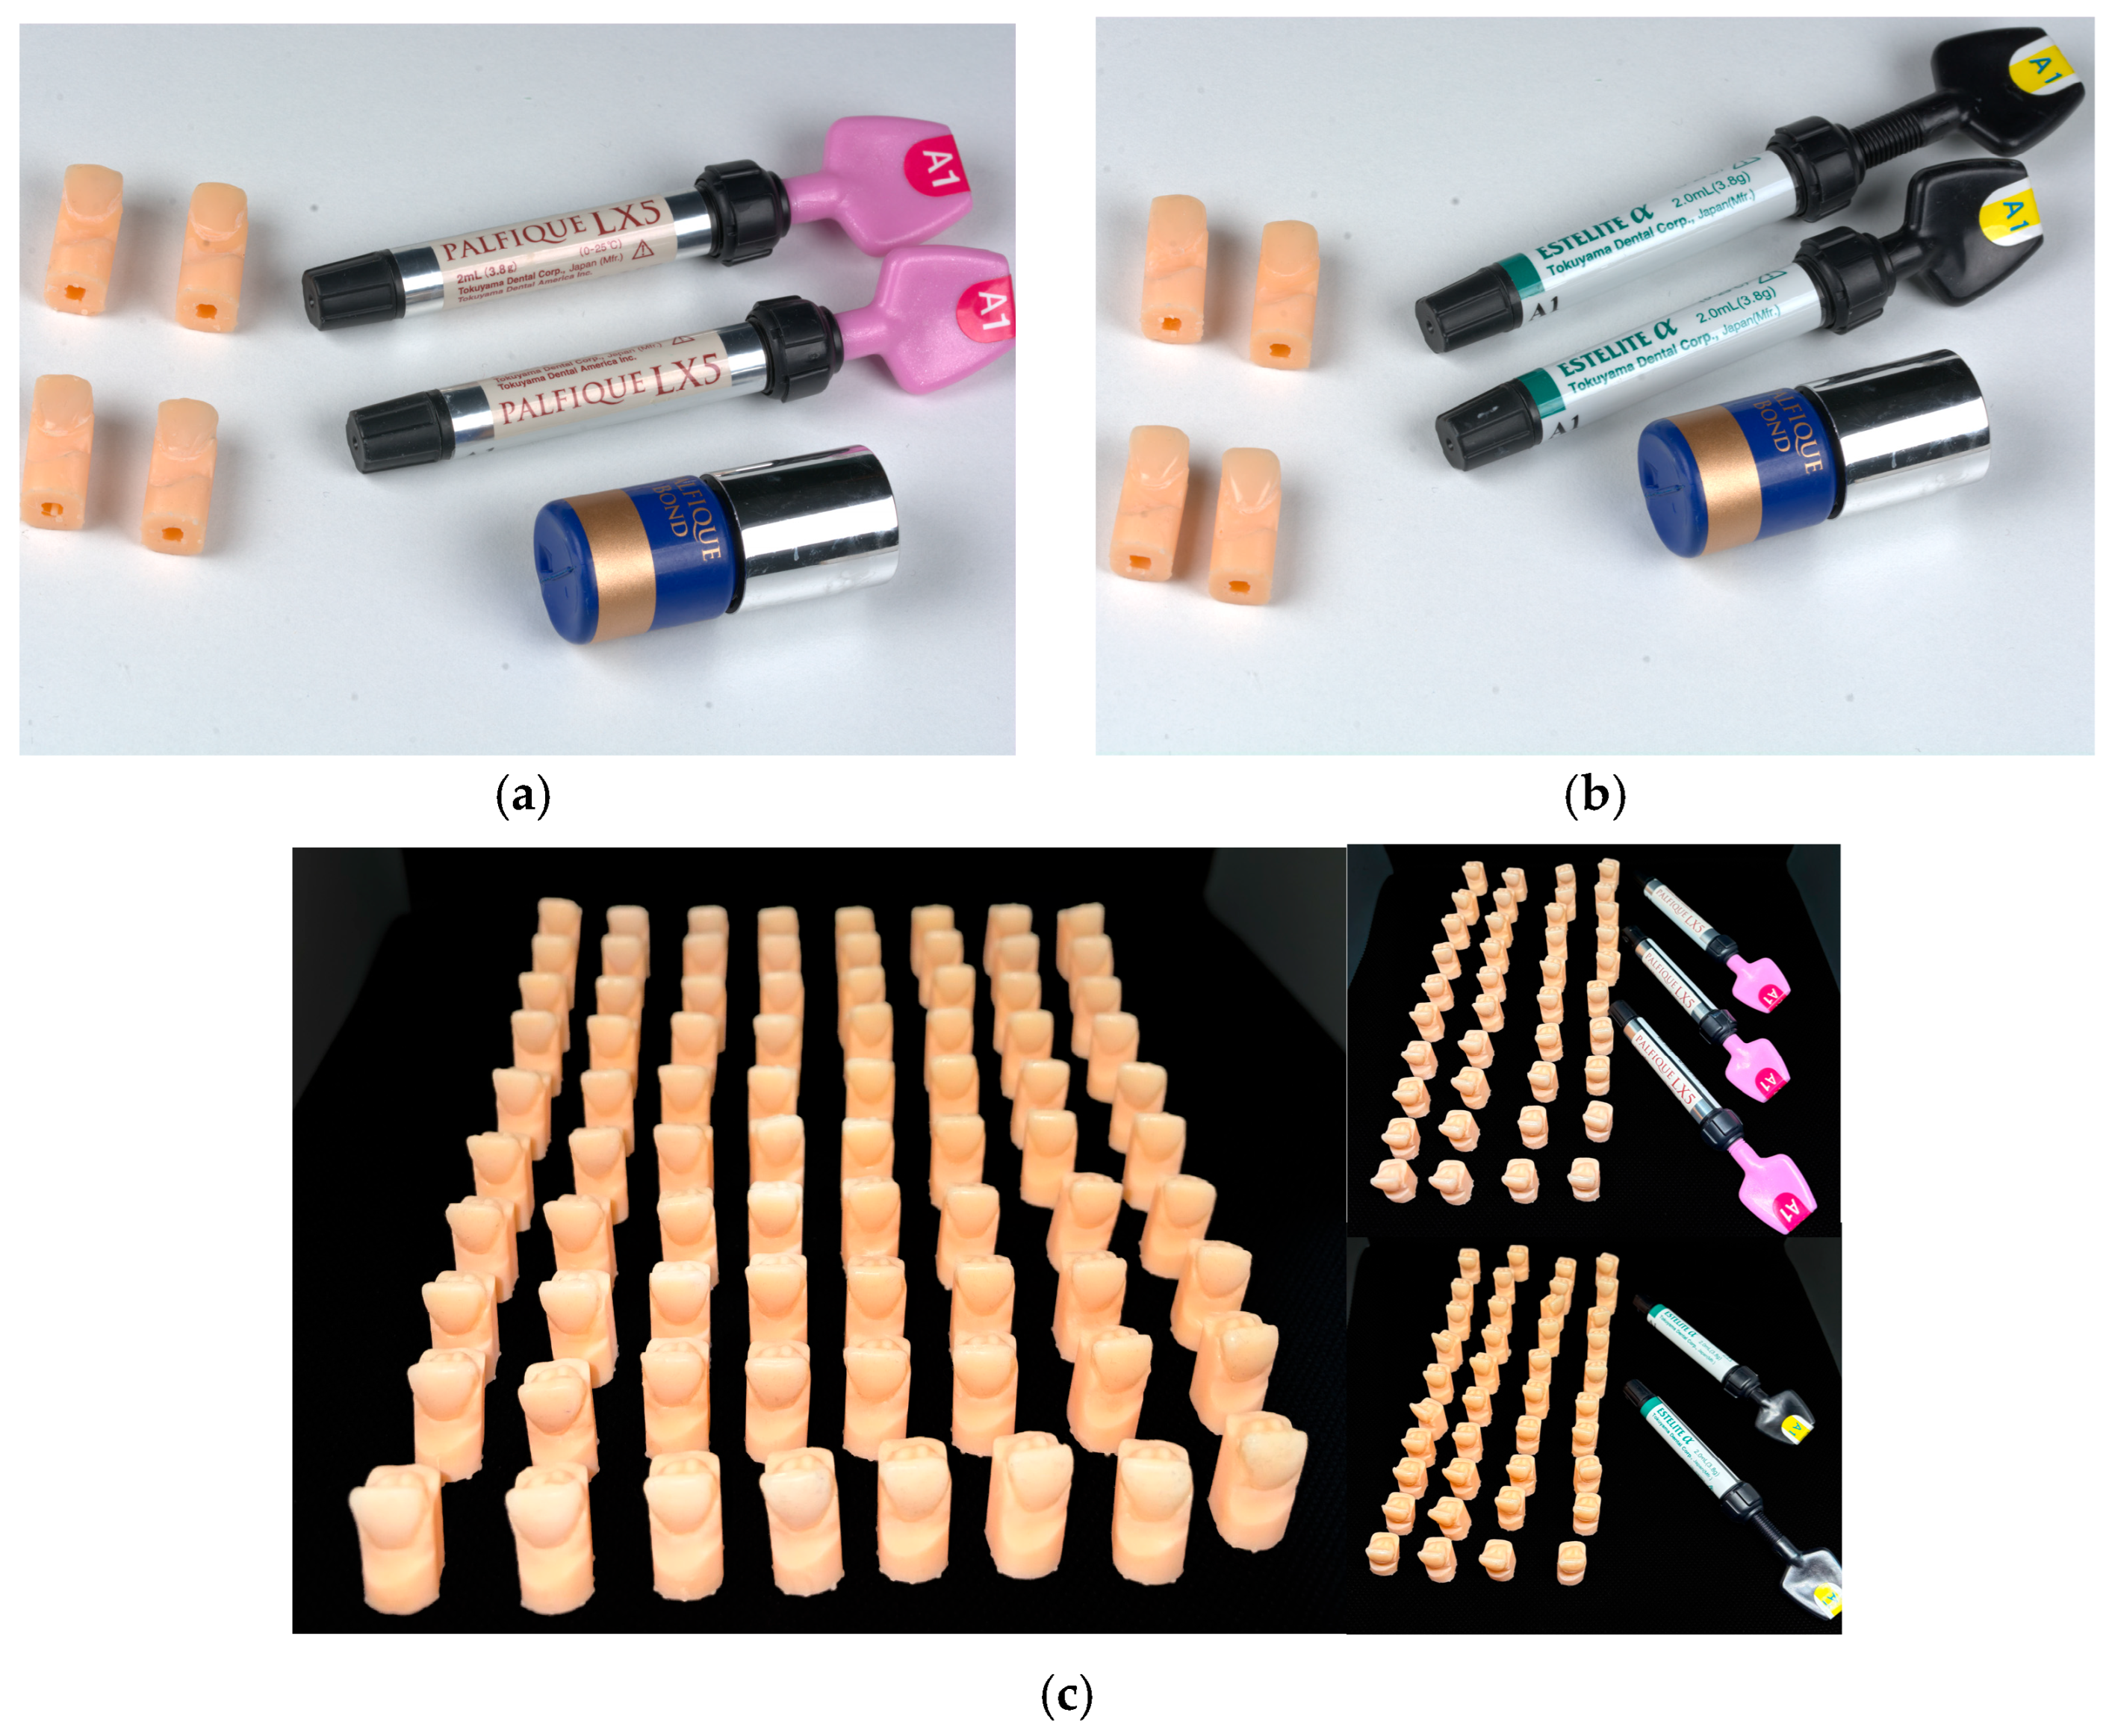
To determine the composite materials and polishing systems to be used, a survey was conducted among dental centres and private clinics well known for providing direct veneer restorations. To eliminate proprietary bias, a universal bonding agent and composite materials from a single manufacturer were utilised. Tokuyama Universal Bond was applied to each sample and light-cured according to the manufacturer’s recommendations. The samples were divided into eight groups (n = 10) and restored with A1-shade, Bis-GMA-based, supra-nanospherical-filled composite resins. The first four groups (G1–G4) were restored with PALFIQUE® LX5 (Tokuyama Dental, Tokyo, Japan). The remaining groups (G5–G8) were restored with Estelite® Alpha (Tokuyama Dental, Tokyo, Japan). The composite was then stamped with the previously prepared clear guide to ensure that all samples possessed identical anatomical contours (Figure 2, Table 2). Finally, the samples were light-cured according to the manufacturer’s recommendations using an LED curing light emitting 900 mW/cm2 (CV-215 CICADA®, Foshan Cicada Dental Instrument Co., Ltd., Foshan, China).

2.3. Polishing Protocol

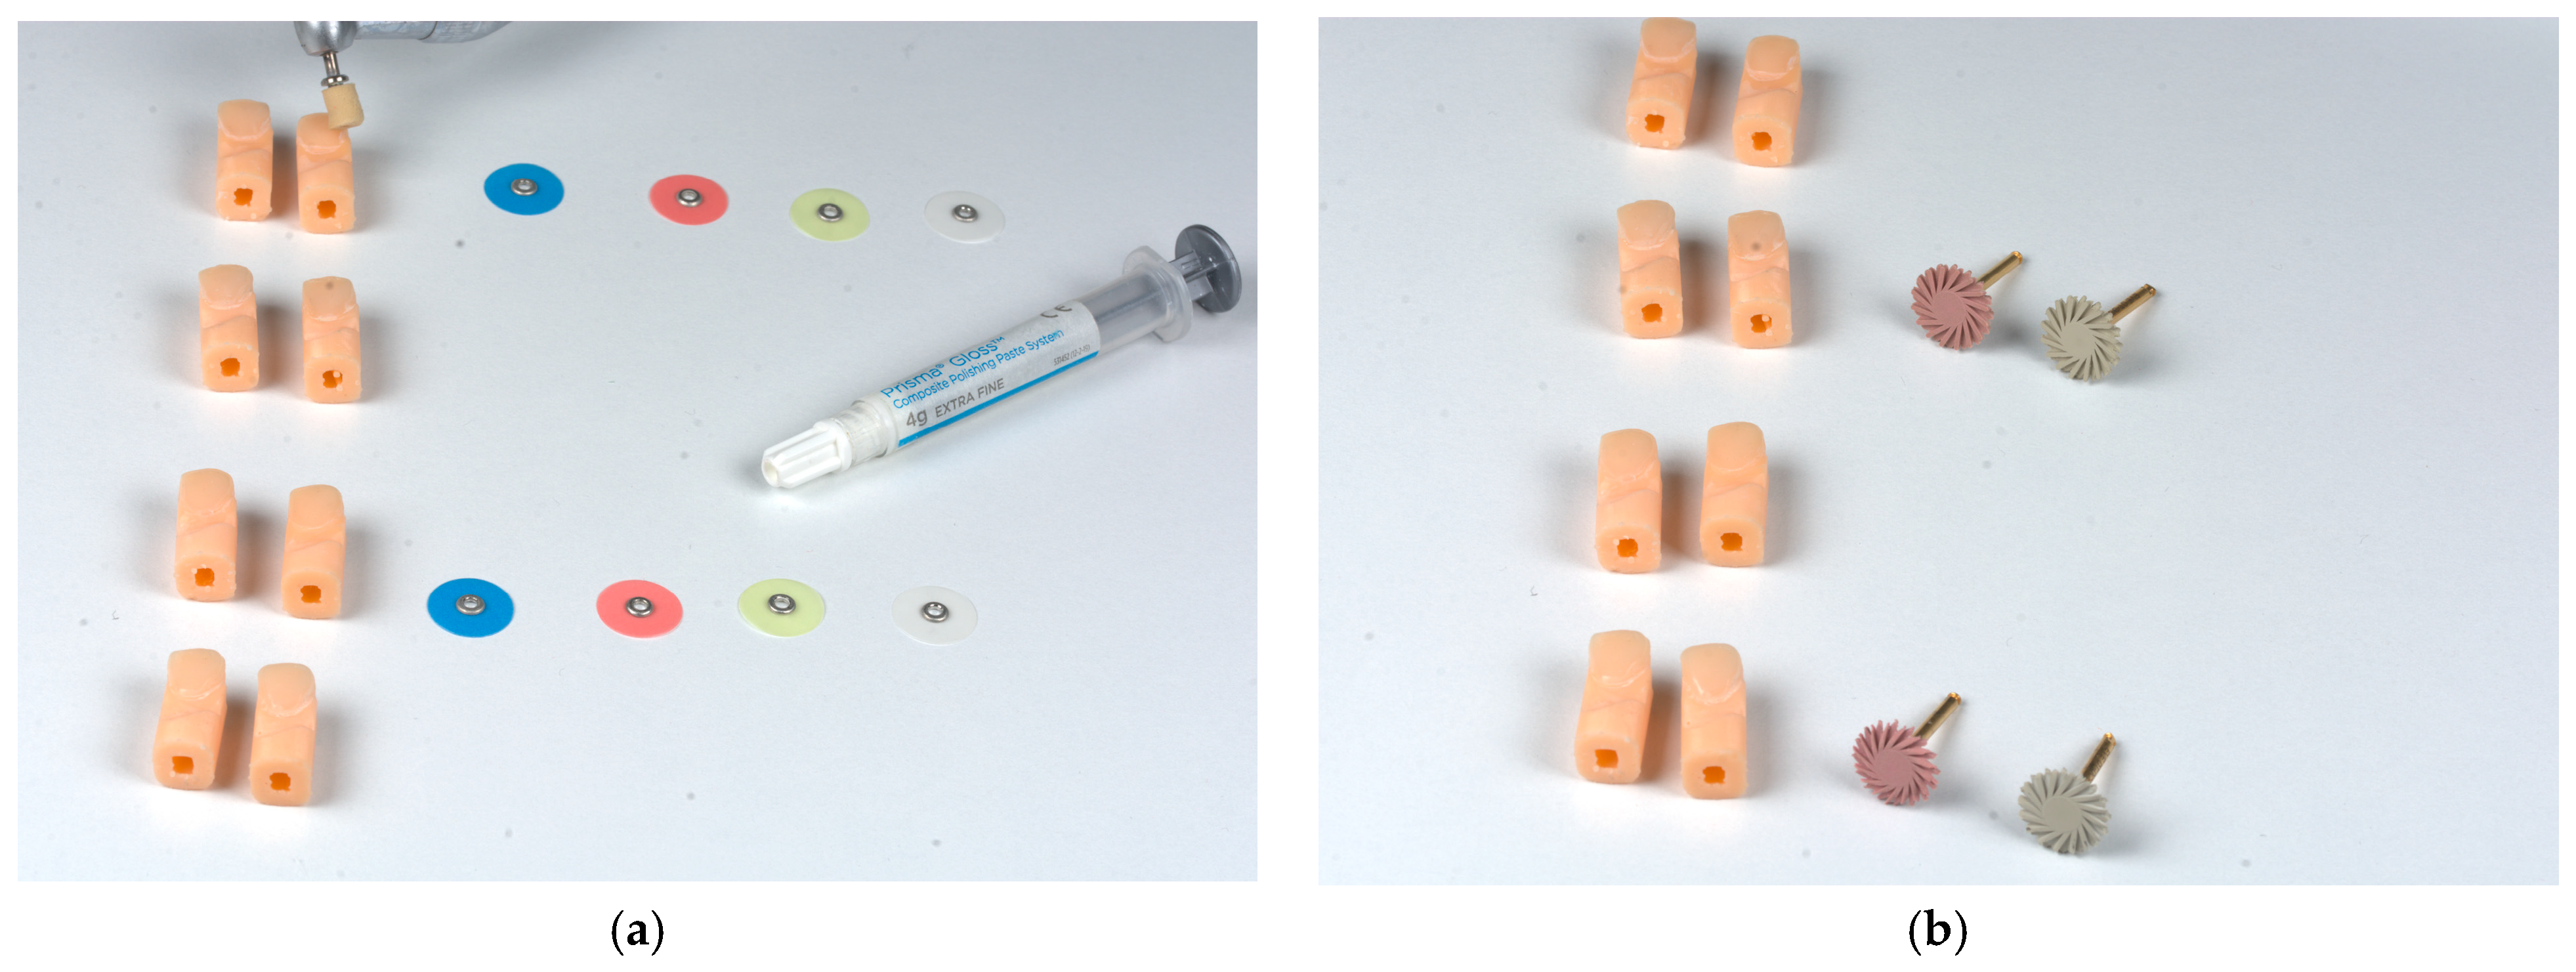
The samples were separated according to the polishing system used. The standard method was selected, as it represents the gold standard for composite polishing. Alongside this conventional approach, a reduced method was chosen, as it has recently been adopted to reduce clinical chair time for patients. For the standard method (Groups 1, 2, 5, and 6), coarse to extra-fine discs (EVE Flexi-D®, EVE Ernst Vetter GmbH, Keltern, Germany) were used, followed by final high-gloss polishing using Enhance® Foam Polishing Cups in conjunction with Prisma® Gloss composite polishing paste (both from Dentsply Sirona, Charlotte, NC, USA). For the reduced method (Groups 3, 4, 7, and 8), medium and fine polishing wheels (EVE Diacomp® Plus, EVE Ernst Vetter GmbH, Keltern, Germany) were used. The polishing methods are detailed in Figure 3 and Table 3. To eliminate inter-operator variability, all polishing procedures were performed by a single trained investigator. Each step was carried out for 30 s across the entire labial surface, strictly adhering to the manufacturer’s instructions. All polishers were applied in a circular brushing motion to simulate clinical use and reduce the risk of scratching or grooving the specimens. To prevent instrument degradation and abrasive wear from acting as confounding variables, a new polisher was used for each specimen in the standard method, while a new polisher was employed for every five specimens in the reduced method. Polishing was performed at a standard speed of 10,000 rpm (5000 rpm for the foam polishing cup) driven by air pressure (45 psi), which was monitored via the dental unit’s pressure gauge. This was accompanied by a water coolant directed perpendicularly to the labial surface of the samples. An overview of the study protocols is illustrated in Figure 4.

2.4. Colour Measurement Protocol

All spectrophotometric evaluations were conducted by a single investigator. This ensured standardisation and control for environmental interference. To minimise operator bias, all 80 specimens were anonymised with numerical codes prior to measurement. This ensured that group identities were not immediately obvious during the spectrophotometric procedures. Measurements were taken under midday natural light. A neutral grey background was utilised in accordance with ISO specifications. Prior to each group measurement, the spectrophotometer (VITA Easyshade® V, VITA Zahnfabrik, Bad Säckingen, Germany; 5 mm tip diameter) was calibrated. This procedure was performed strictly according to the manufacturer’s recommendations using the provided white reference tile. Baseline colour parameters (L, a and b) were recorded from the centre of each specimen (T1).
Measurements of colour were assessed through L*, a* and b* parameters: L* evaluates lightness, a* represents the green–red axis, and b* signifies the blue–yellow axis. Their alteration results were mathematically obtained through a colour calculator (Bruce Lindbloom calculator).
To ensure mathematical accuracy, all colour alterations (∆E00) were verified using the Bruce Lindbloom colour calculator. The standard CIEDE2000 formula was utilised to mathematically calculate all colour differences:
Δ E 00 = Δ L K L S L 2 + Δ C K C S C 2 + Δ H K H S H 2 + R T Δ C K C S C Δ H K H S H
To interpret the clinical significance of these findings, the calculated colour differences (ΔE00) were evaluated against internationally accepted 50:50% consensus thresholds for dental colour research (Table 4).

2.5. Staining Protocol

Regarding the type of immersion solution, tea is one of the most widely consumed daily beverages worldwide, with a widespread tendency to add sugar to the plain solution. To isolate the specific chromogenic impact of sucrose, conventional control groups (such as distilled water) and alternative acidic beverages (such as coffee or red wine) were intentionally excluded. Black tea was selected as the primary staining medium because it contains high concentrations of polyphenols. Furthermore, excluding acidic beverages like red wine prevented erosive organic acids from confounding the specific polyphenol–sucrose interaction. Literature regarding whether sucrose alters the statistical outcomes of the same immersion solution remains limited. Therefore, evaluating the same immersion medium under two distinct conditions was favoured for this study. Following the baseline measurements, the samples were incubated for 24 h at a temperature of 37 °C. They were then stored in dark containers containing a black tea immersion solution (Special Blend, Ahmad Tea Ltd., Hampshire, UK), as shown in Figure 5, which was prepared by adding two standard tablespoons to 1 L of boiled water in a tea kettle and simmered over low heat for 10 min according to the manufacturer’s instructions [21]. Subsequently, sugar was added to the tea solution for the even-numbered groups to replicate realistic daily human dietary consumption at a concentration of 3.33% (w/v) (10 g of sucrose per 300 mL of brewed tea) [18]. Staining solutions were replaced every 24 h for 28 days based on established in vitro literature [22], with the concentration and temperature of the solutions standardised each time they were replaced.

2.6. Treatment Protocol

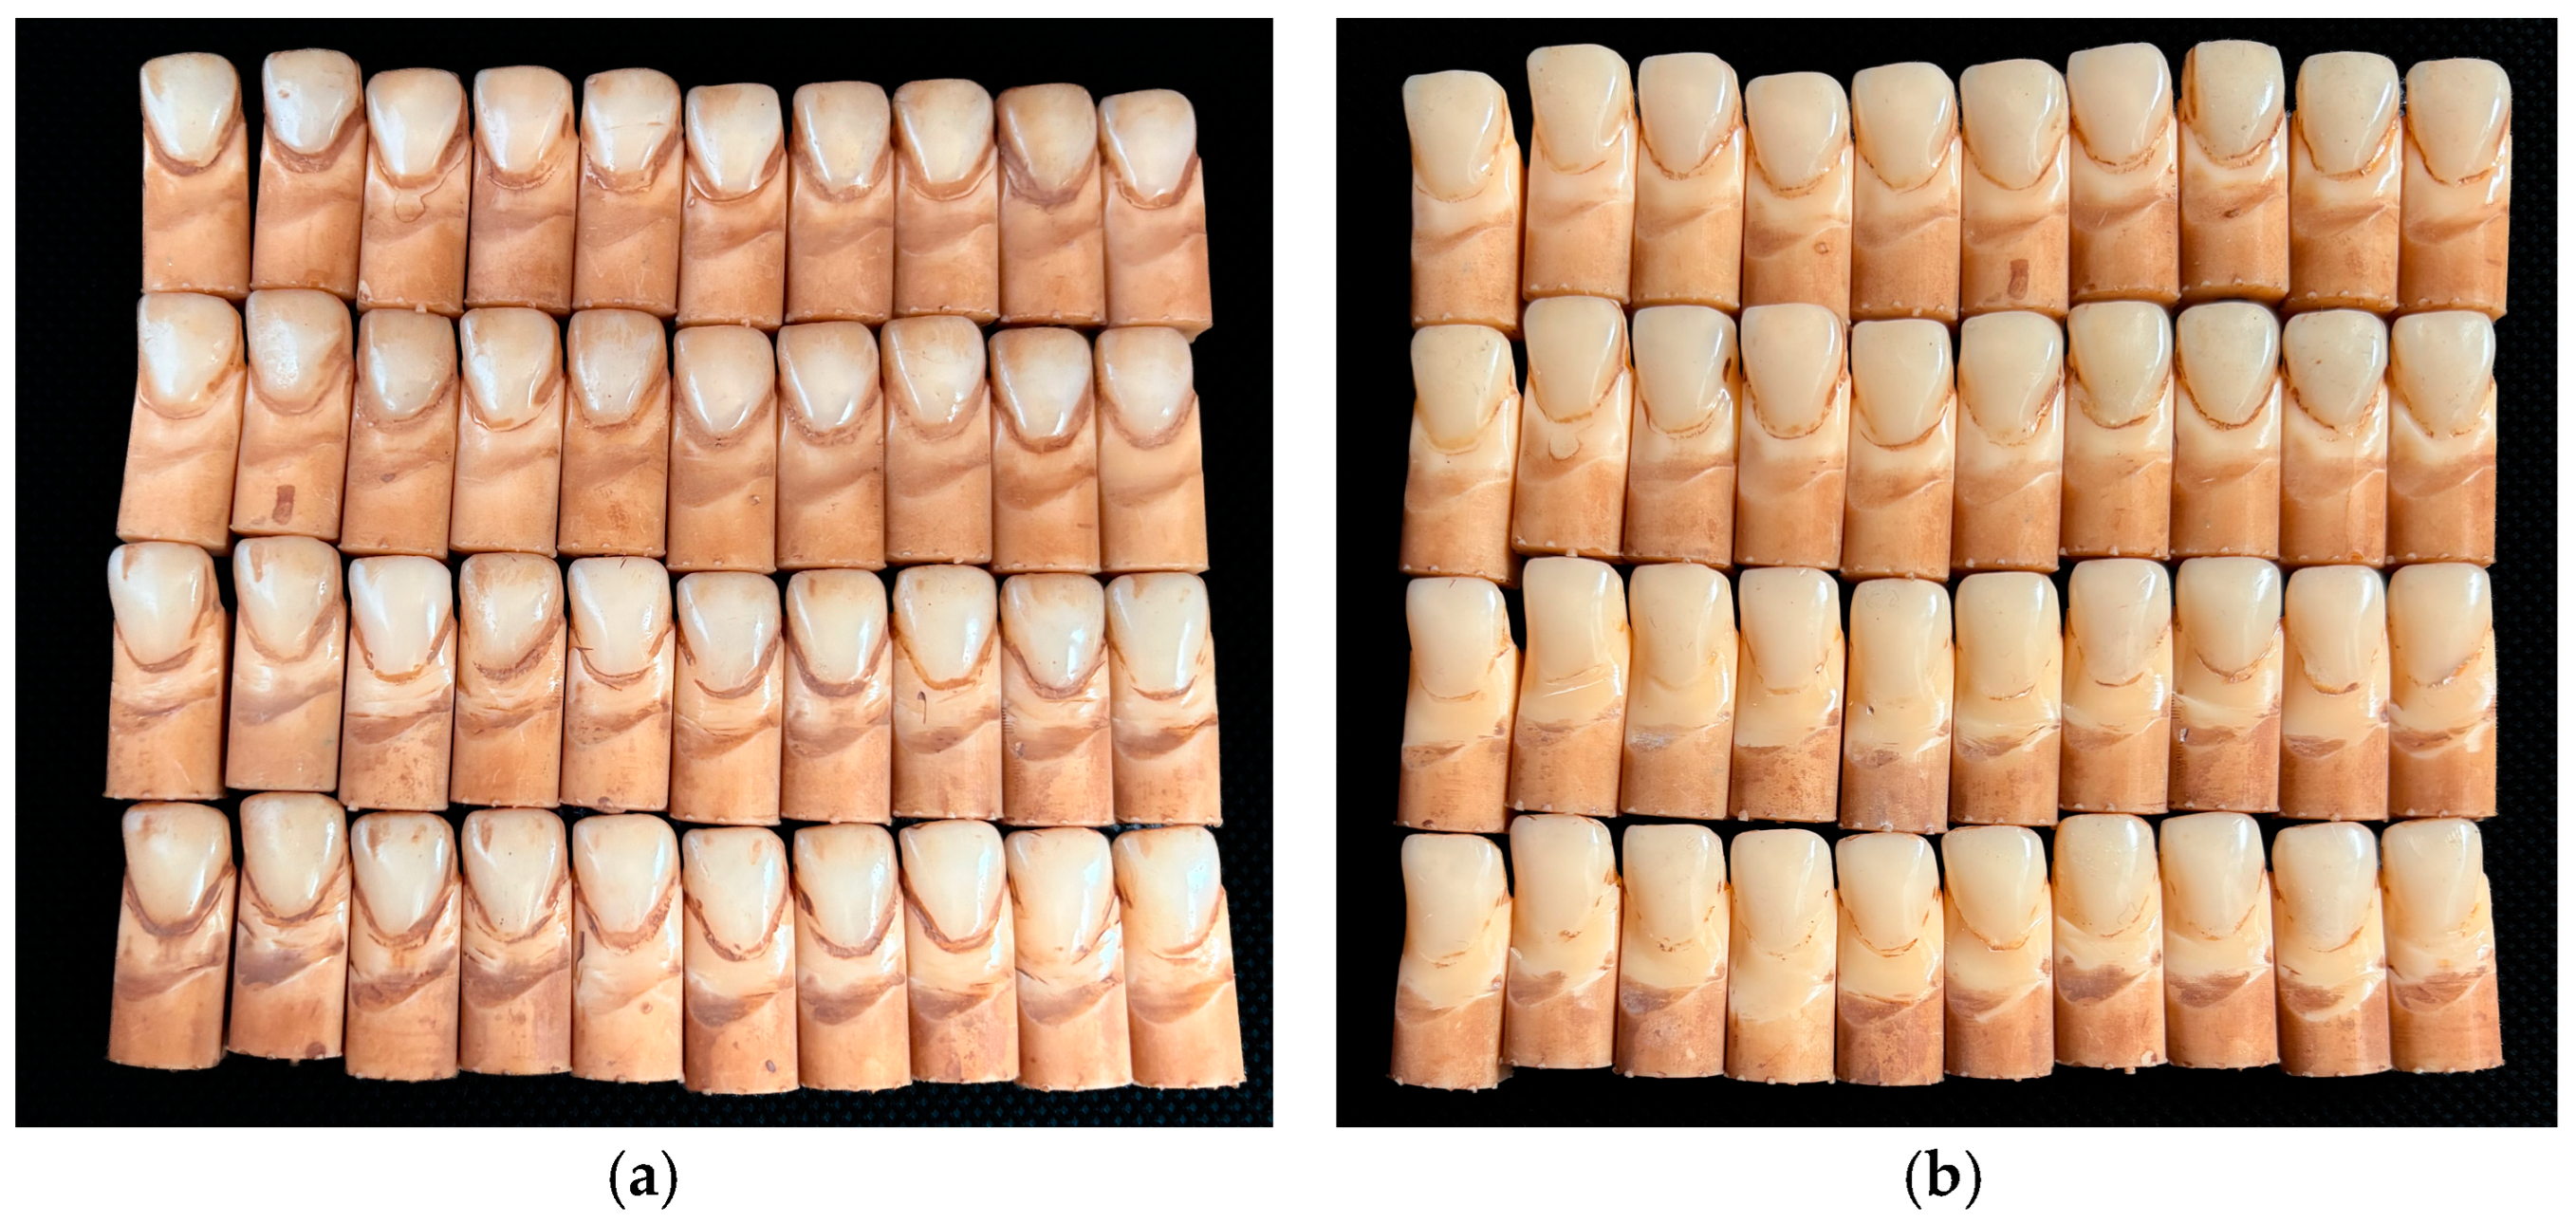
Following the completion of the immersion period, the samples were rinsed with distilled water for two minutes and dried (Figure 6a). The second set of colour measurements (T2 and ∆E001) was recorded. The samples were then repolished using the same polishing systems previously employed (Figure 6b). Subsequently, the third set of measurements (T3 and ∆E002) was obtained to assess the influence of the two polishing systems. Finally, ∆E003 was calculated to evaluate the overall recovery of the samples.

2.7. Statistical Analysis

Statistical analysis was performed using IBM SPSS Statistics version 25.0 (IBM Corp., Armonk, NY, USA). A Shapiro–Wilk test was conducted to assess data normality, which confirmed that the data were normally distributed. Subsequently, a repeated-measures mixed ANOVA was performed to analyse the effects of composite type, polishing procedure, staining solution, and their interactions over the time intervals of the experiment on colour stability. Pairwise comparisons were evaluated using the Bonferroni correction. To enhance clinical interpretation, effect sizes were calculated and reported as partial eta-squared (η2) alongside p-values, and 95% confidence intervals (CIs) were generated. The threshold for statistical significance was strictly maintained at α = 0.05 for all tests.

3. Results

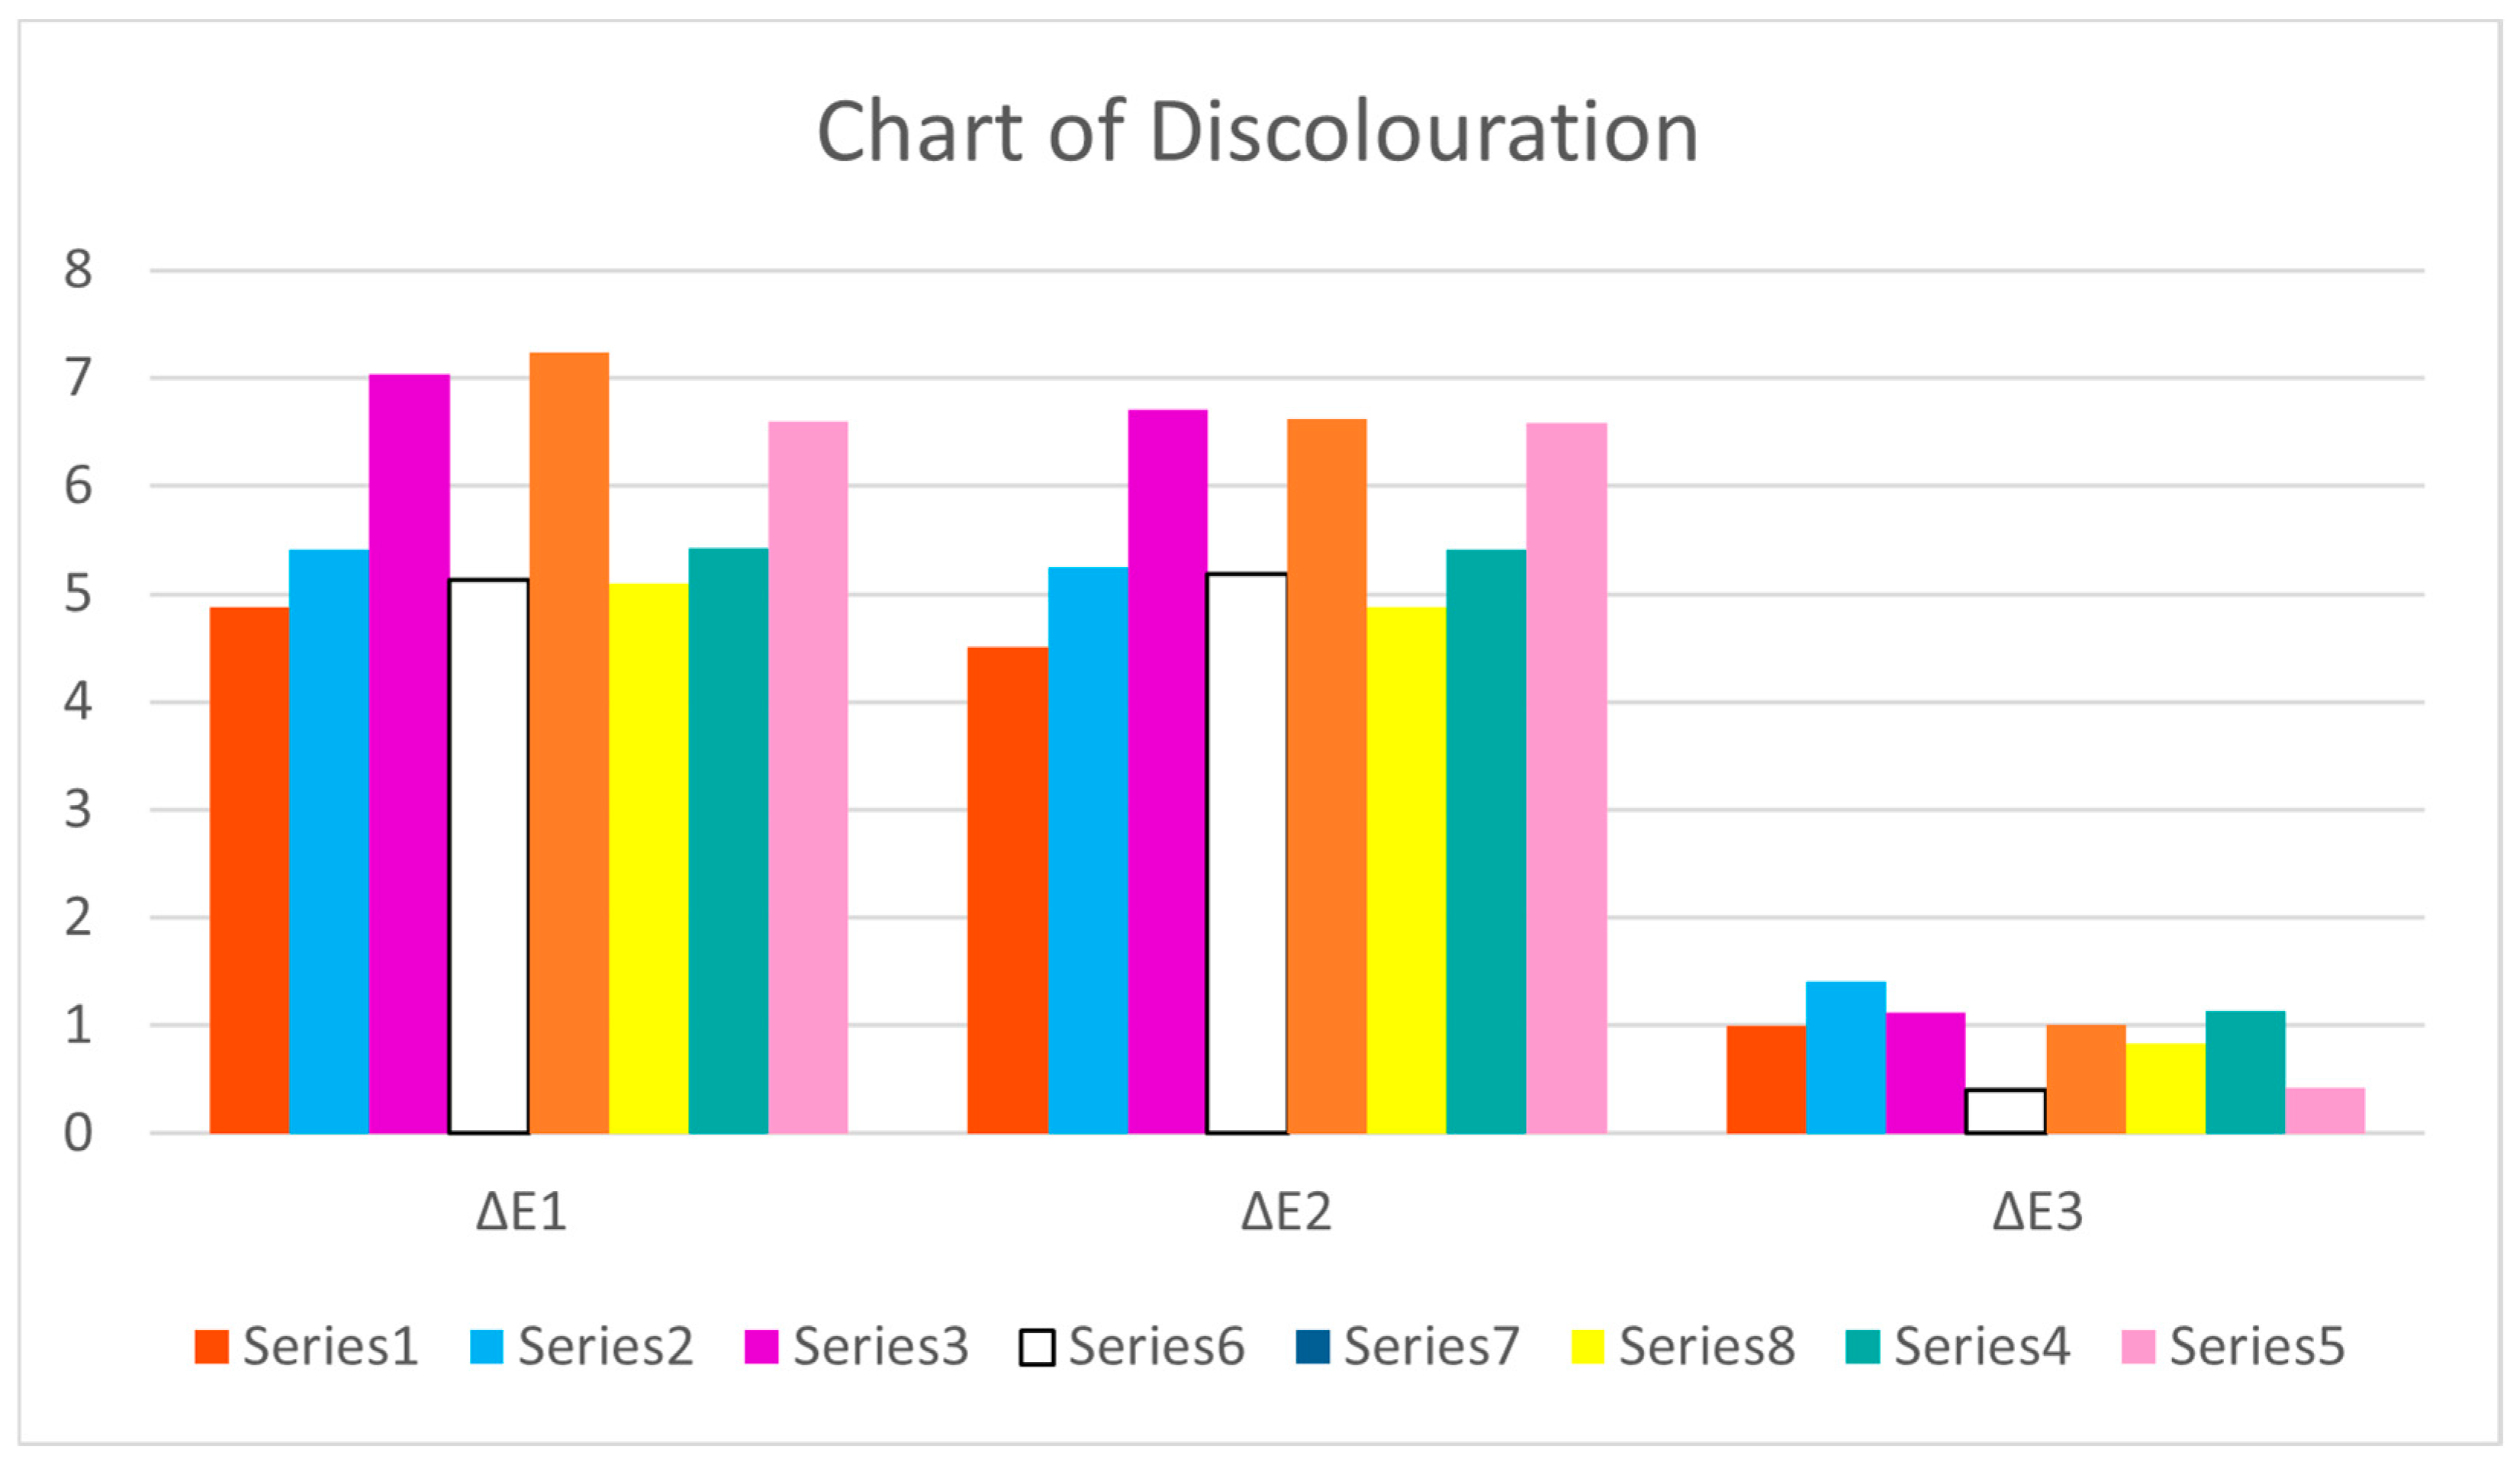
The colour stability of the direct veneer restorations was evaluated across three distinct phases. Initial staining (ΔE001) represented the colour shift from baseline to after immersion. Treatment effect (ΔE002) represented the colour change caused by the repolishing protocol. Finally, colour recovery (ΔE003) represented the net difference between the baseline and the post-treatment phase (Figure 7). To interpret the clinical relevance of these shifts, all outcomes were evaluated against established CIEDE2000 visual thresholds. These included the 50:50% perceptibility threshold (PT = 0.8) and acceptability threshold (AT = 1.8). Descriptive statistics for all eight experimental groups are summarised in Table 5. Data normality was confirmed via the Shapiro–Wilk test. Subsequently, group differences were assessed using a three-way repeated-measures mixed ANOVA at a significance level of p < 0.05. Pairwise group comparisons were conducted using Bonferroni post hoc adjustments. Finally, the linear relationship between initial stain accumulation and subsequent removal was evaluated using the Pearson correlation test.

3.1. Initial Staining (∆E001)

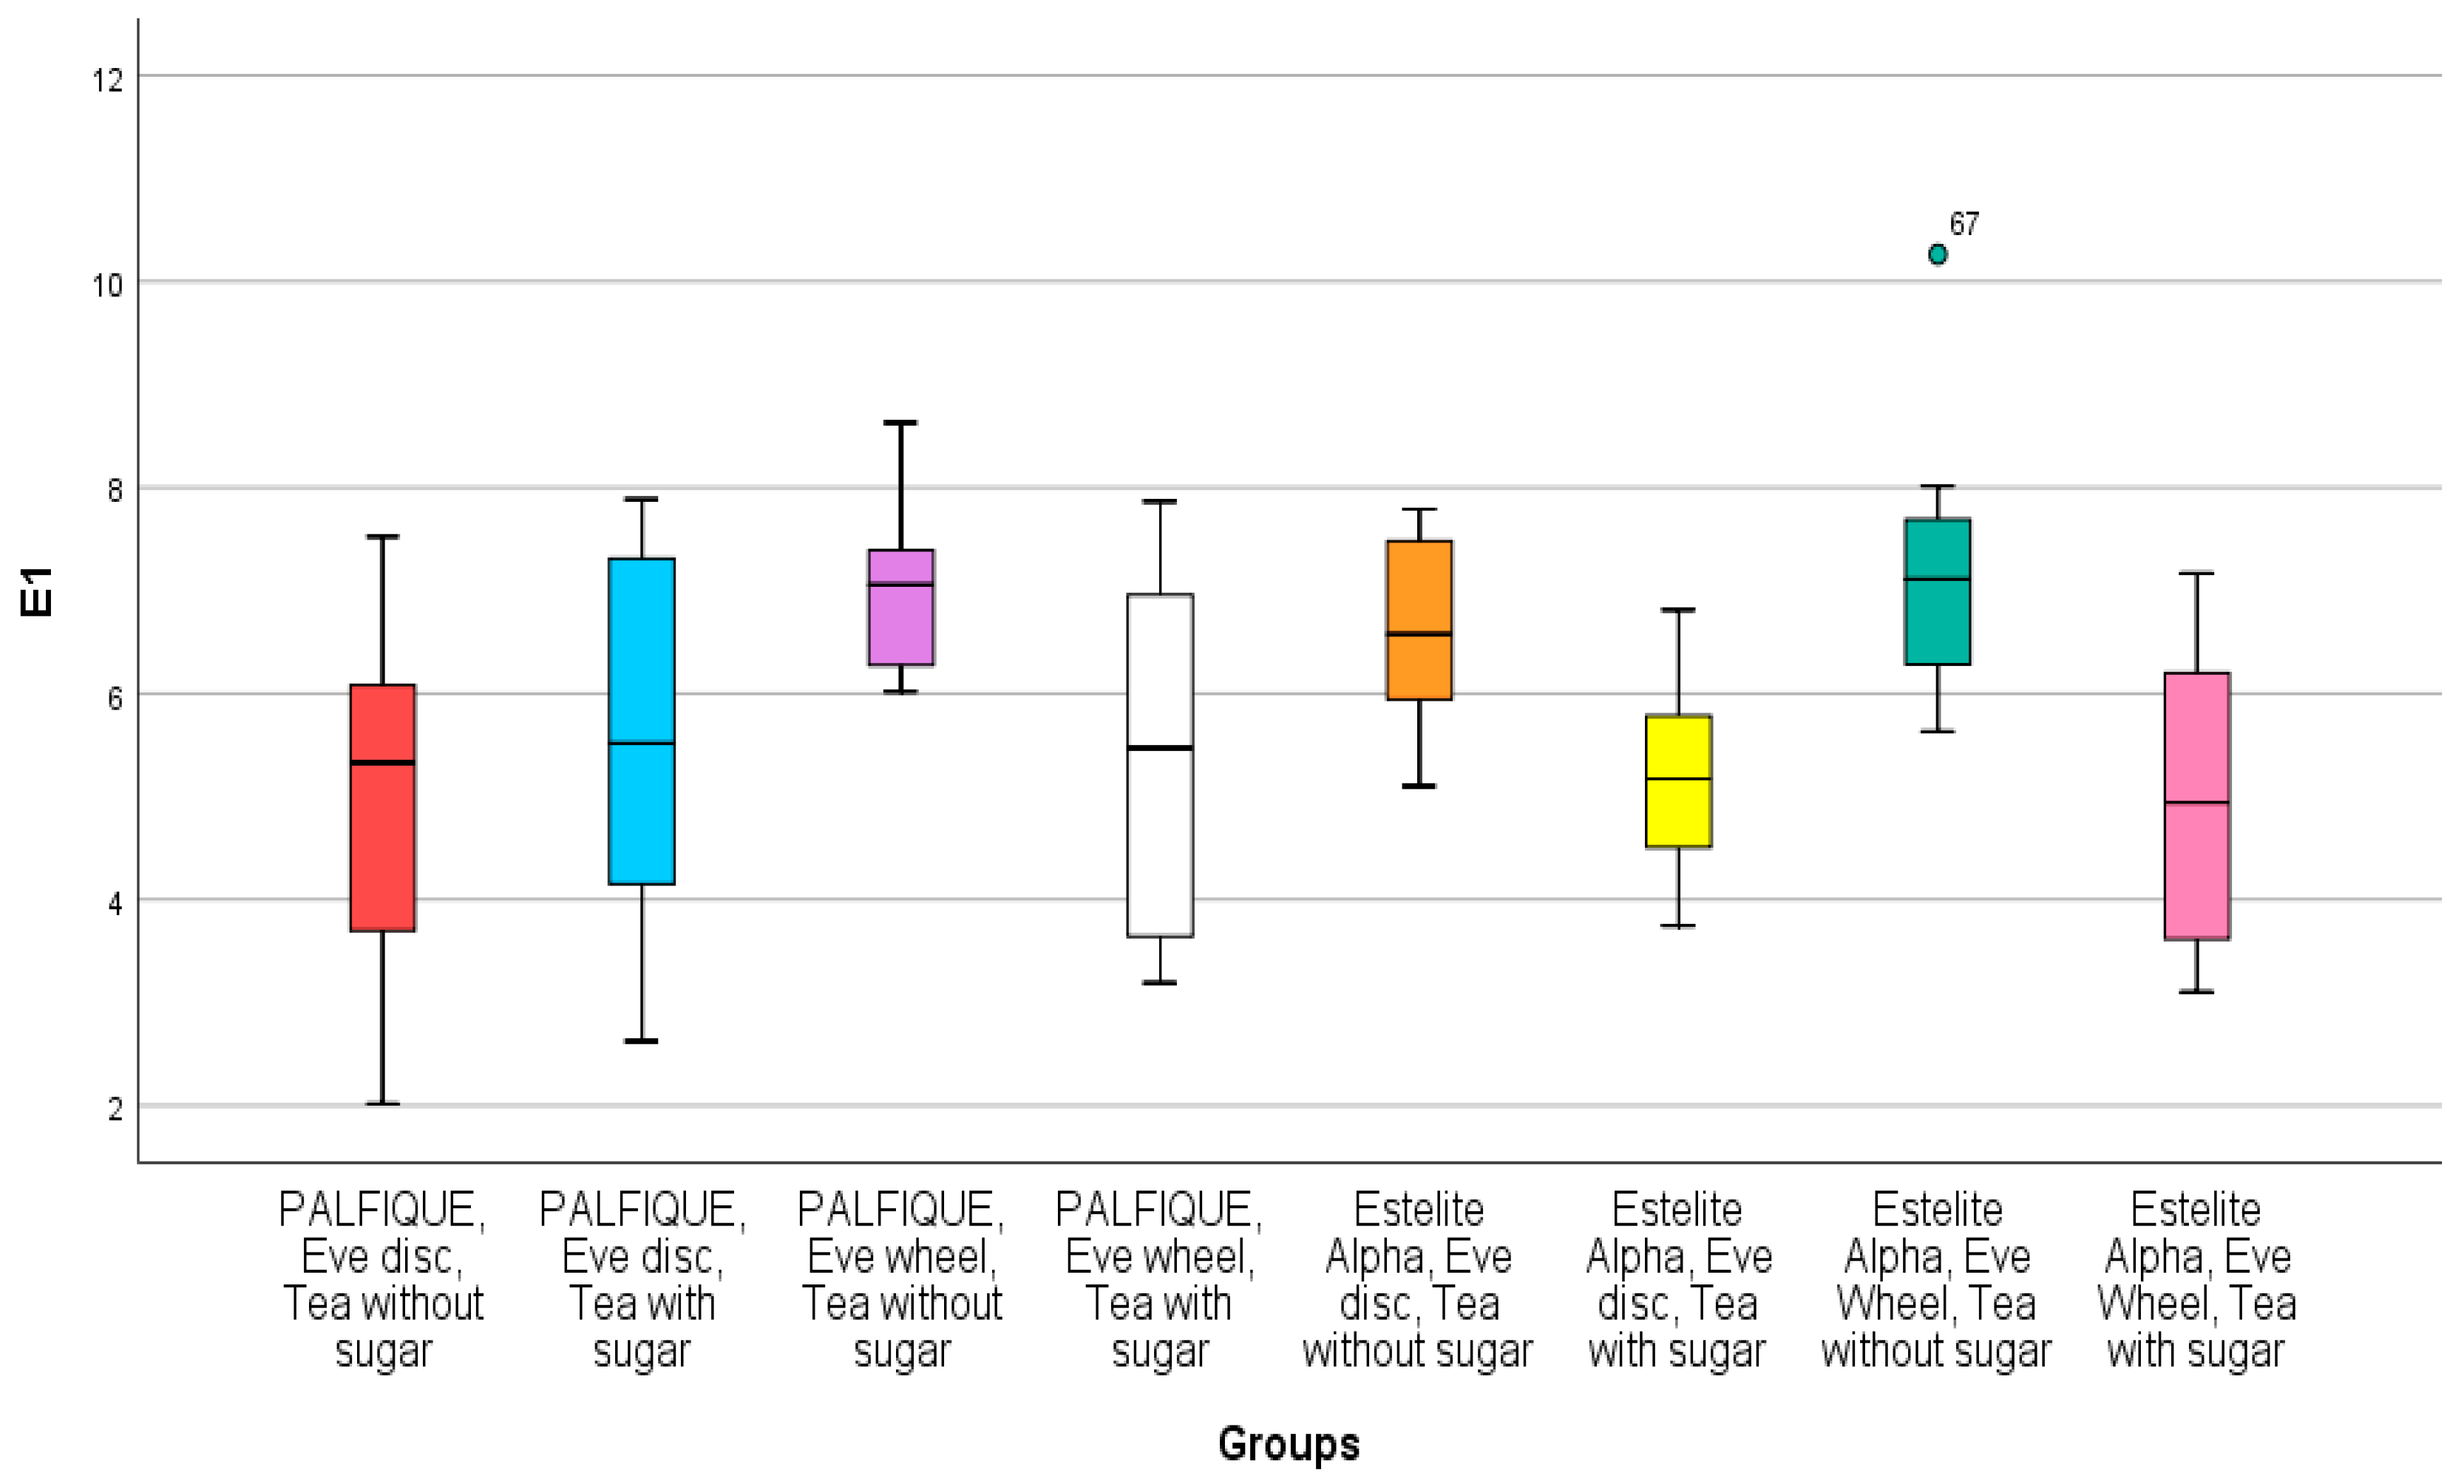
Following 28 days of immersion, all experimental groups exhibited substantial initial colour alterations. These initial shifts significantly exceeded the clinical acceptability threshold (ΔE001 > AT). Both composite types demonstrated comparable susceptibility to initial discolouration. However, specimens prepared with the standard polishing method exhibited less initial staining than those prepared with the reduced method. Regarding the immersion medium, plain tea resulted in substantially higher initial stain accumulation compared to the sucrose-sweetened tea. Detailed descriptive means for initial staining across all groups are provided in Table 5 and Figure 8.

3.2. After Treatment (∆E002)

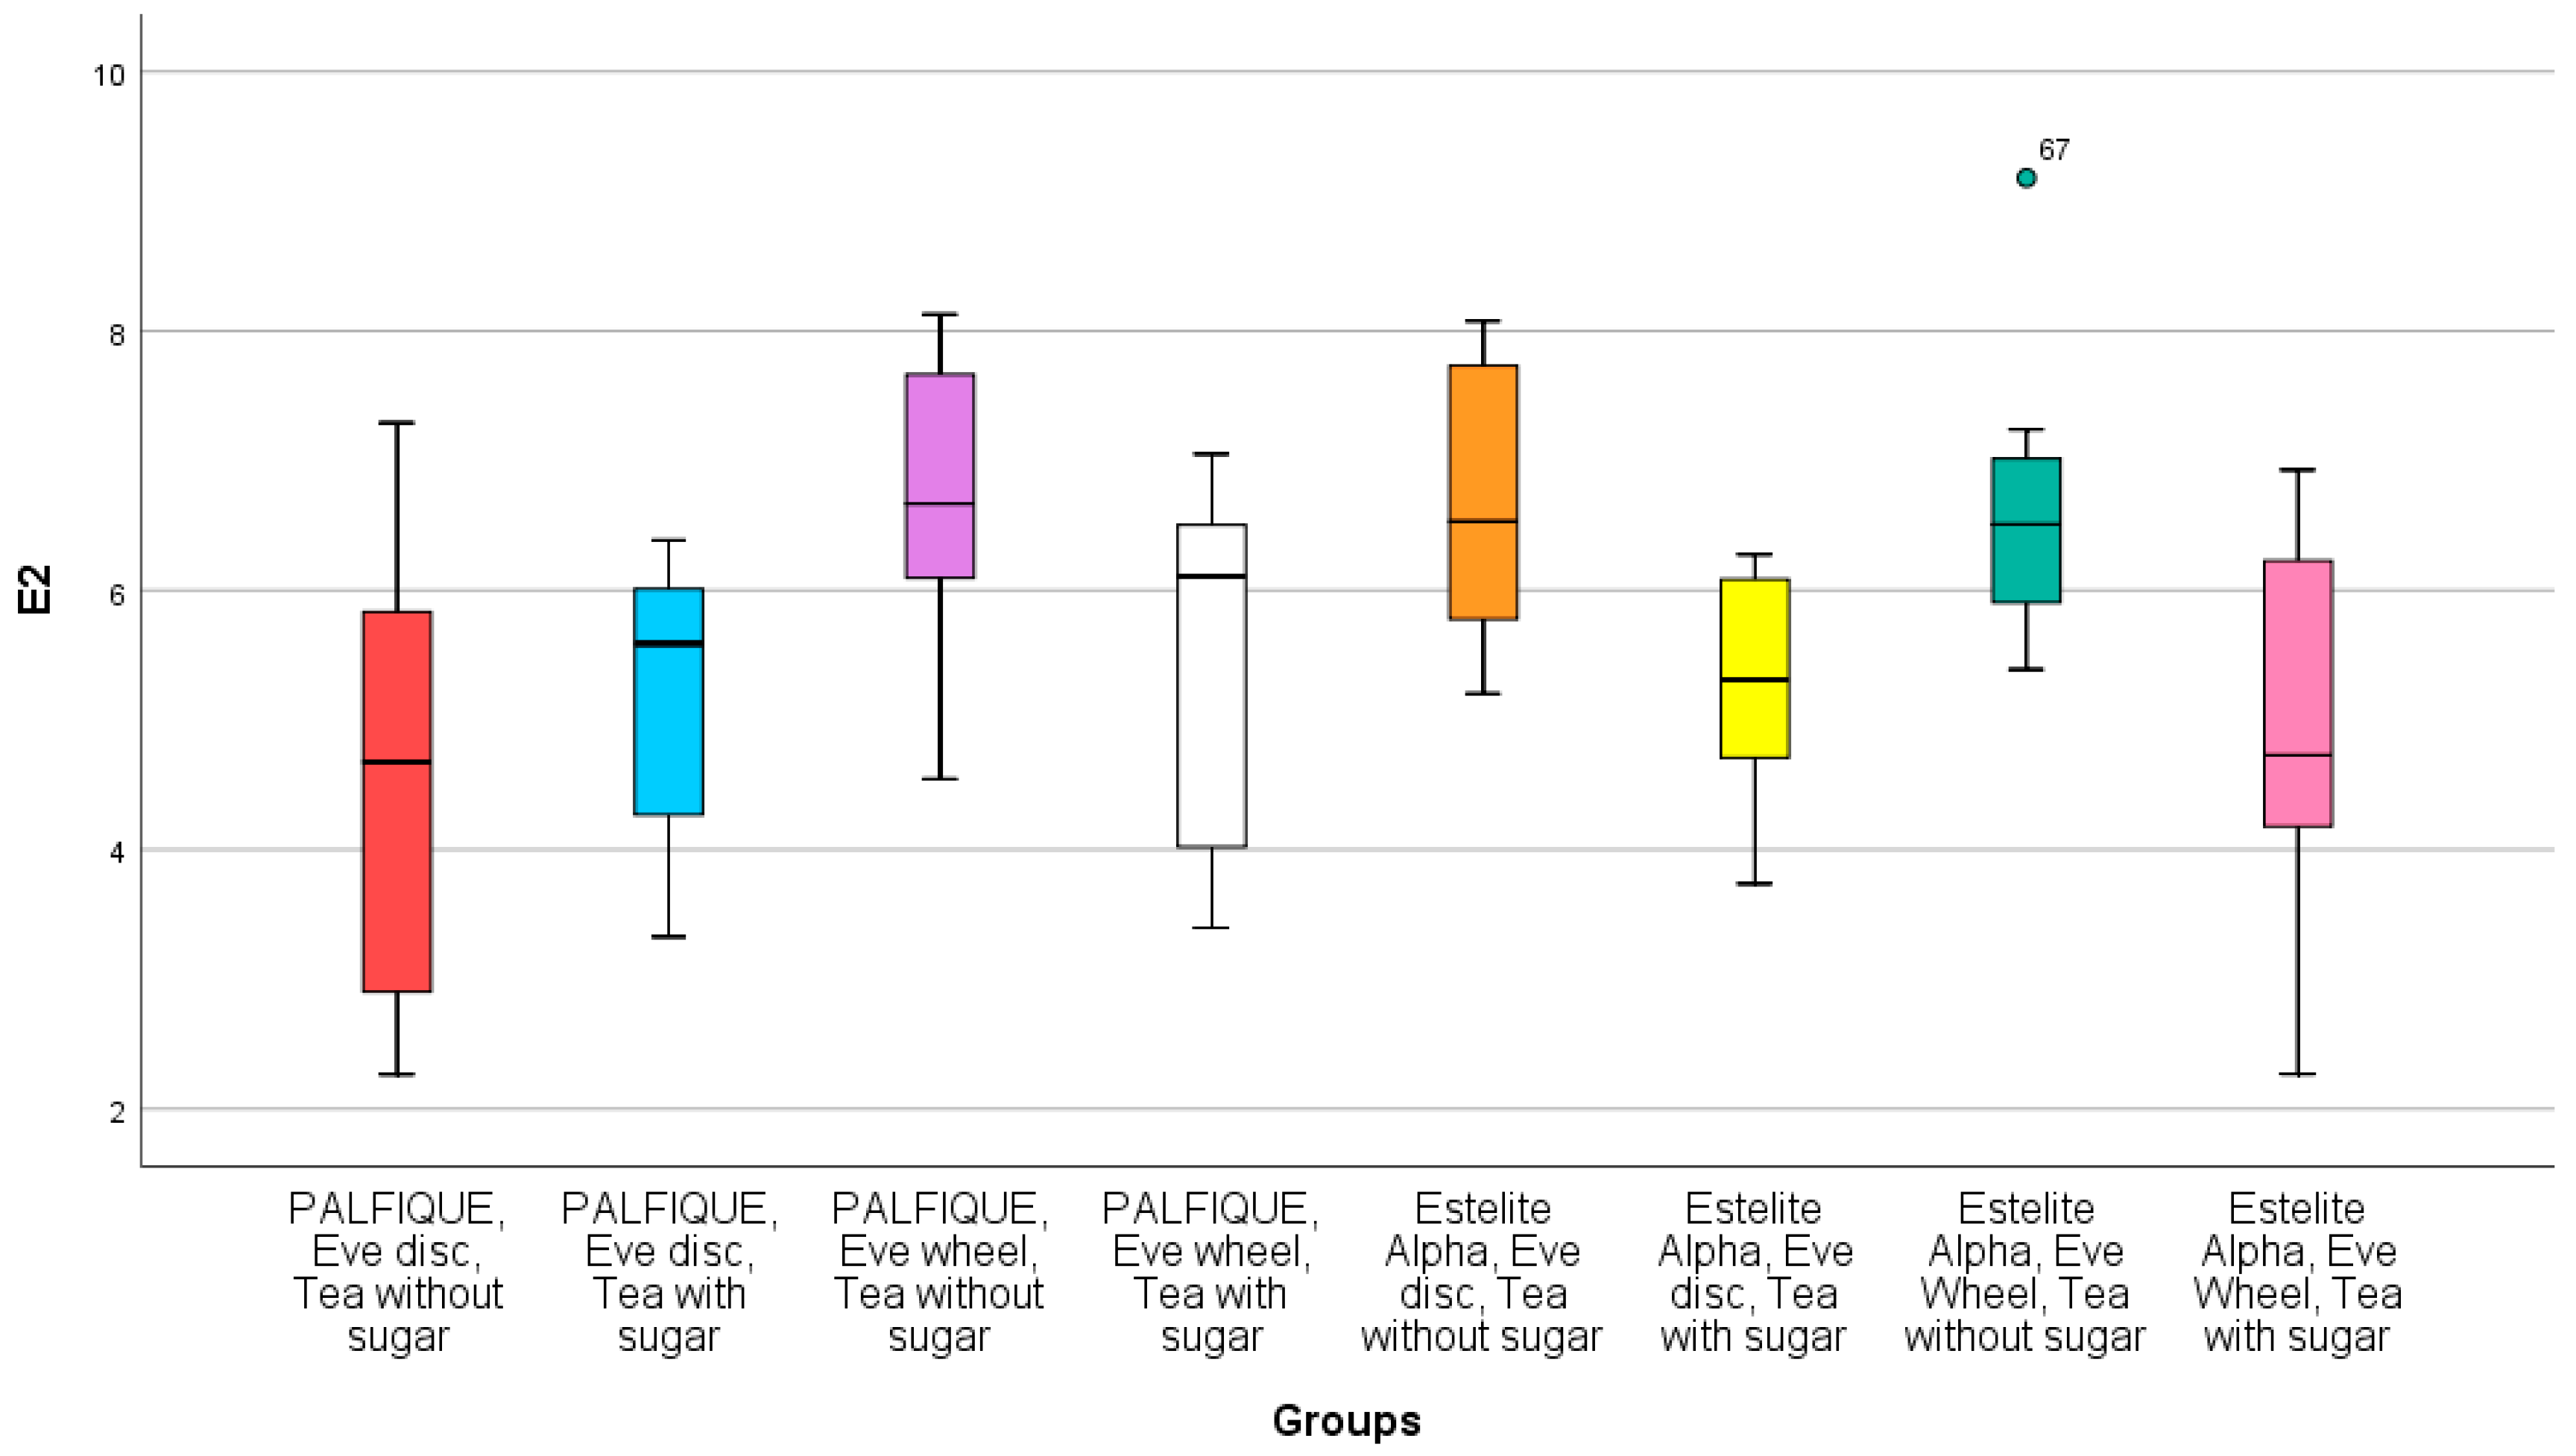
Active mechanical repolishing induced marked colour shifts across all experimental groups. The standard polishing method consistently removed more accumulated colour than the reduced method. Regarding the immersion solutions, samples immersed in plain tea exhibited greater colorimetric shifts during repolishing compared to those immersed in sweetened tea. Both composite materials responded similarly to the active treatment phase. Comprehensive treatment shift values are presented in Table 5 and Figure 9.

3.3. Colour Recovery (∆E003)

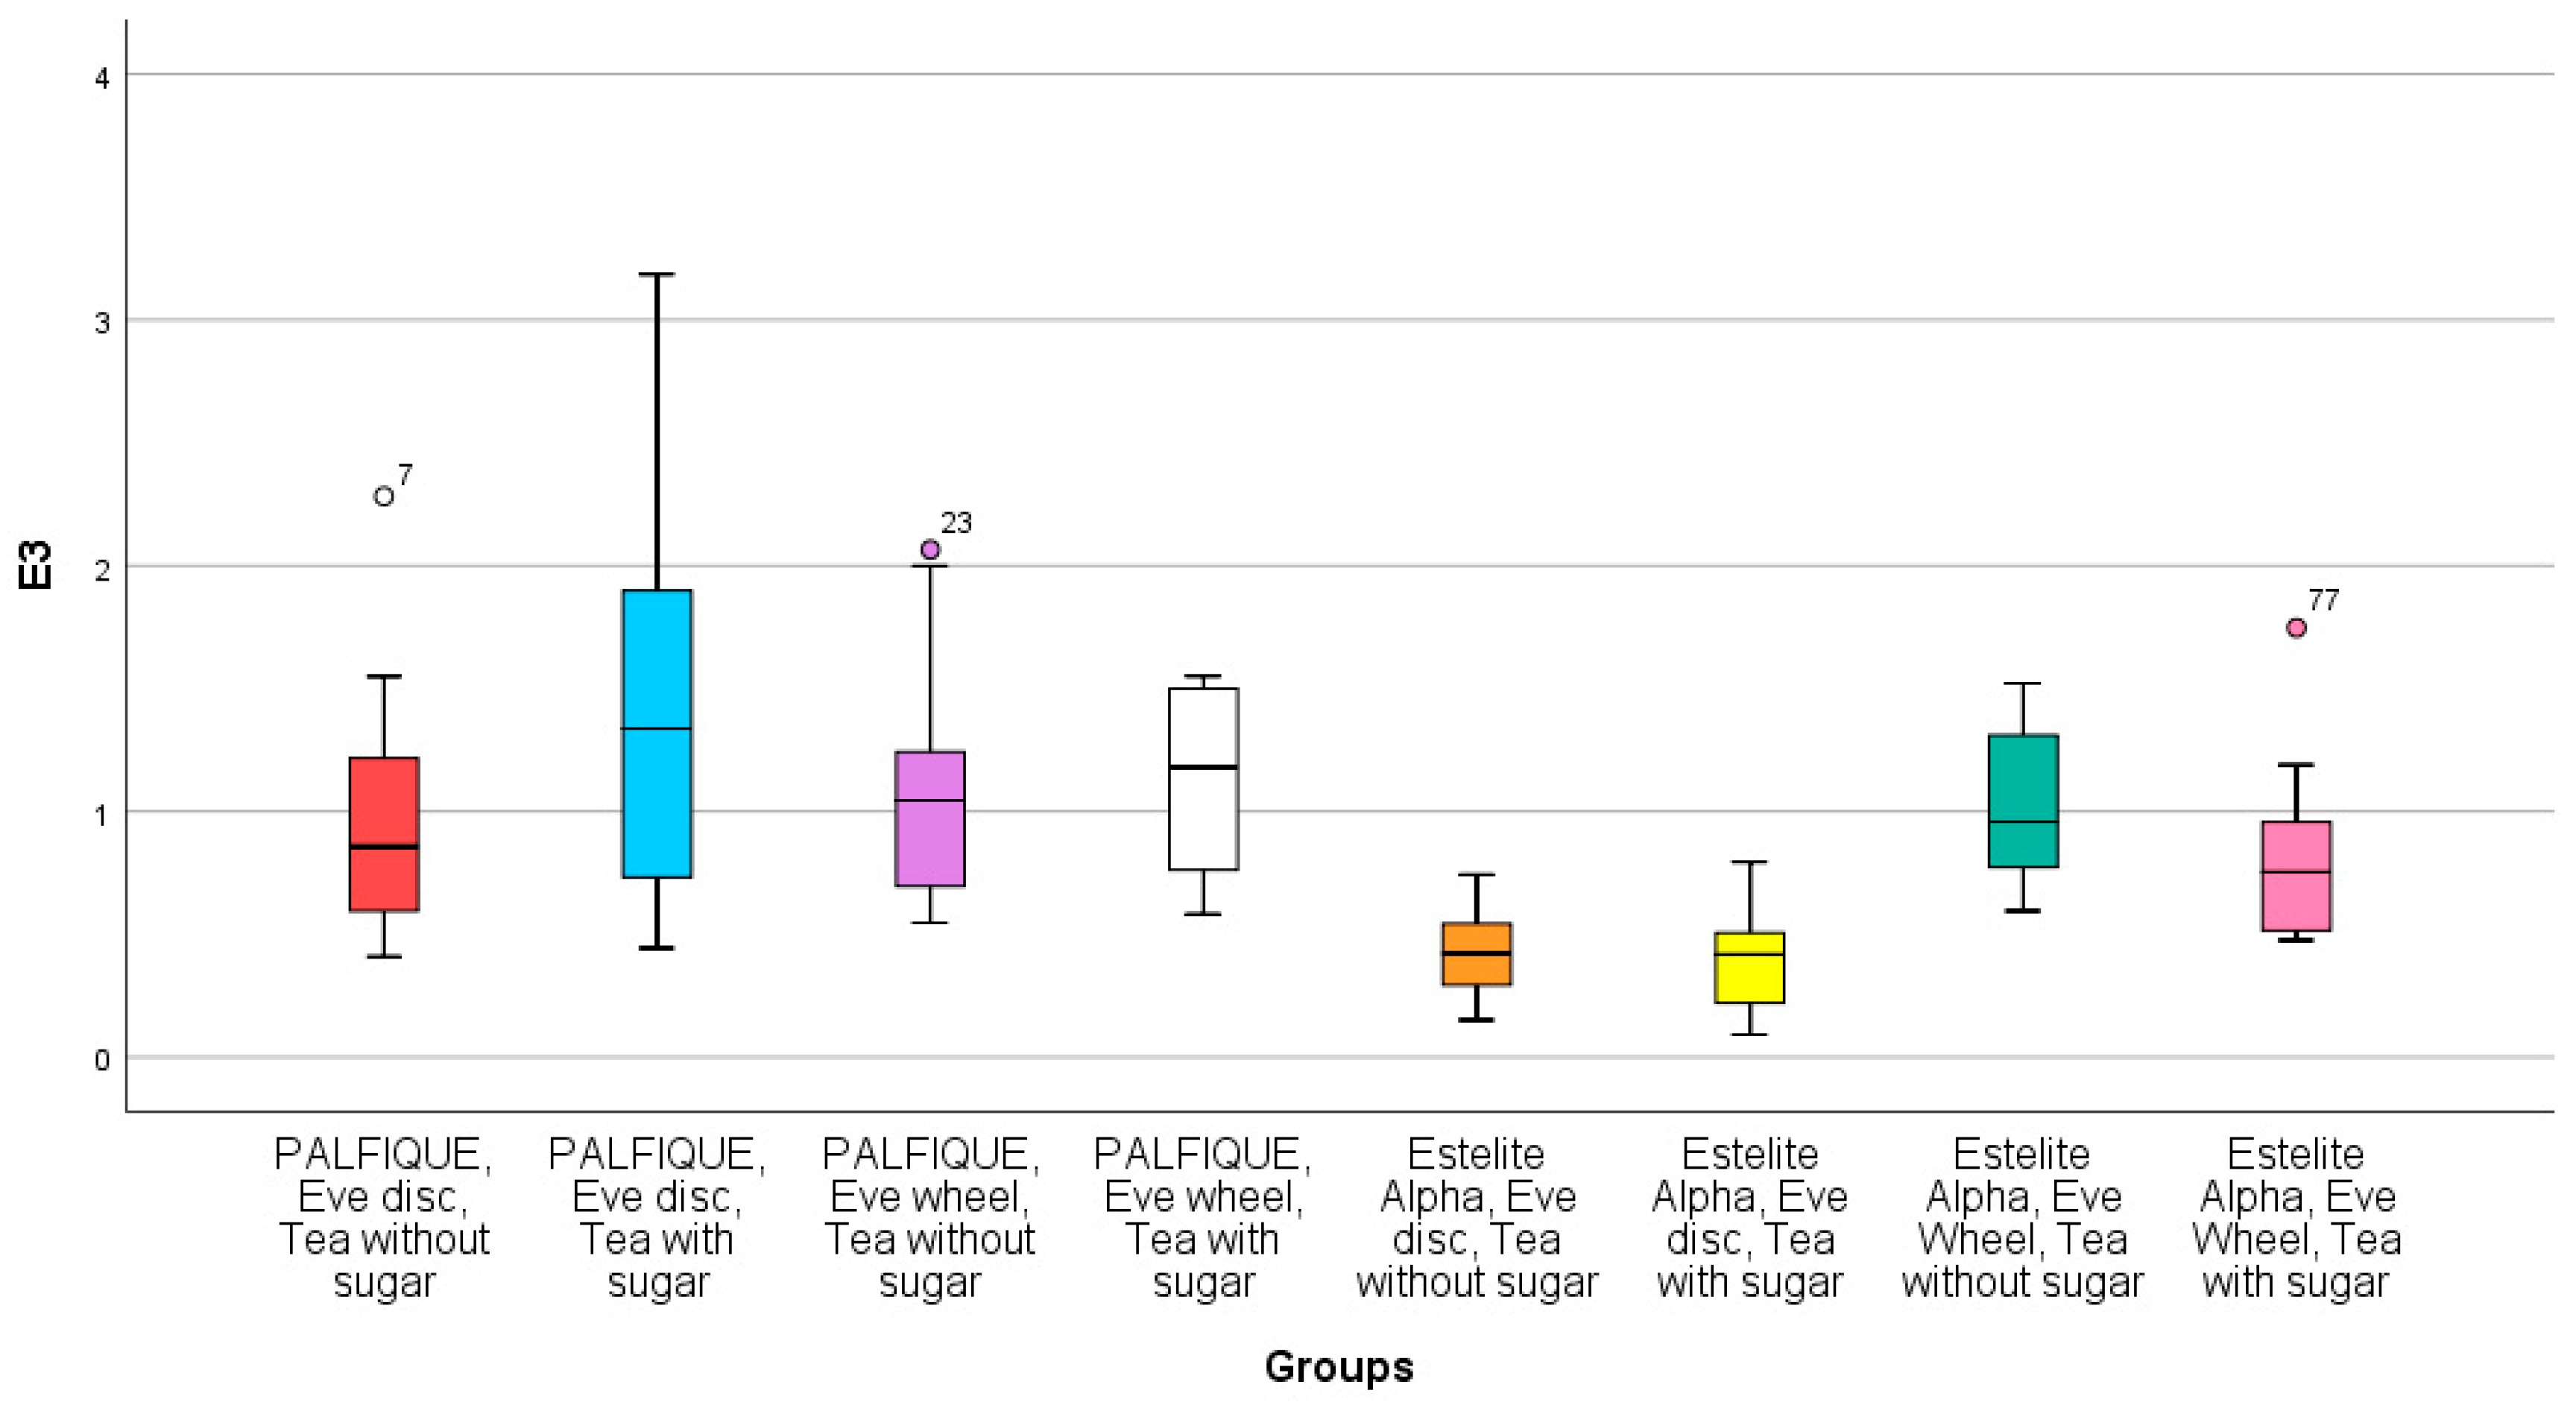
Evaluation of the final residual discolouration revealed that mechanical maintenance was highly effective. It successfully reduced net colour differences to values well within the clinical acceptability threshold (∆E003 ≤ AT) across all composite materials and polishing protocols. While both composites performed well, Estelite® Alpha achieved a final recovery that successfully fell below the perceptibility threshold (∆E003 < PT). The standard polishing method outperformed the reduced method, achieving a net recovery approaching the imperceptible clinical boundary. Conversely, the reduced method left a residual shift that remained above the perceptibility threshold but within acceptable limits (PT < ∆E003 ≤ AT). Immersion in either plain or sweetened tea did not prevent the samples from returning to clinically acceptable colour levels following treatment. Final recovery outcomes are detailed in Table 5 and Figure 10.

3.4. Influence of Composite Materials, Polishing Systems and Immersing Medium

The repeated-measures mixed ANOVA revealed the main and interaction effects governing colorimetric behaviour (Table 6). The composite material alone did not exert a statistically significant main effect on overall colour stability [F (1, 72) = 0.087, p = 0.769, ηp2 = 0.001]. Conversely, a statistically significant main effect was observed for the polishing protocol [F (1, 72) = 5.557, p = 0.021, ηp2 = 0.072]. The standard method consistently resulted in significantly lower overall colour change compared to the reduced method. Furthermore, the immersion medium exerted a statistically significant main effect with a large effect size [F (1, 72) = 11.242, p < 0.001, ηp2 = 0.135].
A significant two-way interaction was identified between composite material and sucrose content [F (1, 72) = 5.500, p = 0.022, ηp2 = 0.071]. A similar significant interaction was found between the polishing method and sugar content [F (1, 72) = 5.537, p = 0.021, ηp2 = 0.071]. In contrast, the two-way interaction between the composite material and polishing system was not statistically significant [p = 0.211]. Finally, the three-way interaction among all combined variables was significant only during the active treatment shift phase (ΔE002).

3.5. Influence of Time

Analysis revealed a highly significant within-subjects time effect on colour alteration [F (1.339, 96.42) = 896.587, p < 0.001, ηp2 = 0.926]. Bonferroni-adjusted pairwise comparisons (Table 7) confirmed that measured colour difference scores decreased significantly across each sequential measurement period.
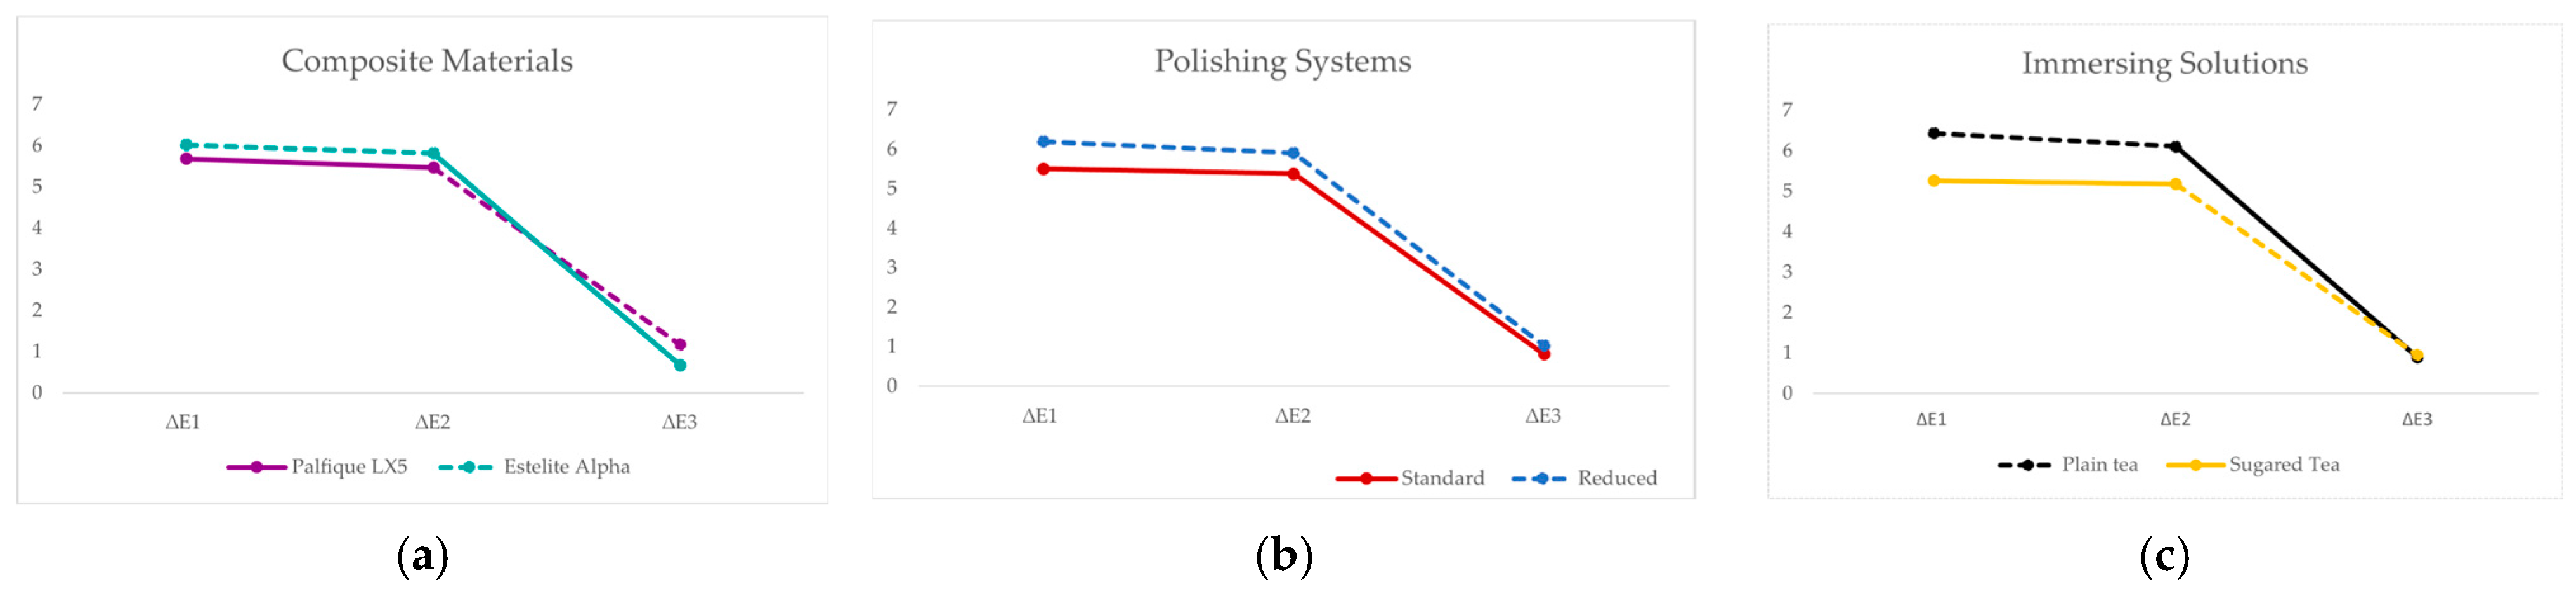
A significant within-subjects two-way interaction was observed between time and composite material [F (1.339, 96.416) = 6.763, p = 0.006, ηp2 = 0.086]. Additionally, a highly significant crossover interaction was found between time and sugar content [F (1.339, 96.416) = 12.14, p < 0.001, ηp2 = 0.144]. Nevertheless, an interaction between time and polishing method was not statistically significant (Figure 11).
Finally, a significant three-way interaction was identified among time, composite material, and polishing method [F (1.339, 96.42) = 7.057, p = 0.005, ηp2 = 0.089].

3.6. Correlation Analysis

A Pearson correlation analysis (r) was performed across the entire dataset. This test assessed the linear relationships among the colorimetric shifts across the three timelines (Table 8). Initial stain accumulation (ΔE001) and the subsequent treatment transition (ΔE002) demonstrated a strong, significant positive correlation. Meanwhile, the final net colour recovery (ΔE003) exhibited no statistically significant correlation with either initial staining severity or active treatment alteration.

4. Discussion

The aesthetic endurance of dental resin-based composites has been suggested to be depend on a complex interaction among dietary chromogenic media, surface micro-topography, and material architecture. This in vitro study assessed these dynamics across three clinical stages. The stages included initial discolouration (ΔE001), treatment alterations after repolishing (ΔE002), and the final outcome of colour recovery (ΔE003).

4.1. Composite Effect

The isolated main effect for the composite materials was not statistically significant. This demonstrates that both PALFIQUE® LX5 and Estelite® Alpha exhibited comparable overall colour stability. Both materials successfully reduced initial discolouration that exceeded the acceptability threshold (ΔE00 > AT) to final residual values well within clinically acceptable limits (ΔE00 ≤ AT). However, a significant time–composite interaction revealed unique material kinetics. Estelite® Alpha experienced greater initial stain uptake yet achieved a final net colour recovery below the perceptibility threshold (ΔE003 ≤ PT). Conversely, PALFIQUE® LX5 stabilised within the acceptable albeit perceptible range (PT < ΔE003 ≤ AT).
When compared to recent systematic reviews on the colour stability of dental composites, these results confirm that modern nanostructured materials offer superior resistance to deep pigment penetration [23]. Historically, many studies using older formulas set the clinical acceptability limit at ΔE ≤ 3.3 [19]. Under modern CIEDE2000 guidelines, the visual acceptability threshold is strictly established at ΔE00 ≤ 1.8. Reassuringly, both investigated materials successfully returned to this modern clinically acceptable range.
One possible explanation for the initial staining phase (ΔE001) is that the hydrophilicity of the resin matrix (e.g., Bis-GMA) dictates early water sorption [8]. This hydrophilicity may be equally attractive to the polyphenolic chemicals in tea [15]. However, when exposed to sucrose, the materials began to behave differently. This may be related to subtle variations in their proprietary monomer–filler coupling or cross-linking density. A plausible mechanism could involve the polymer networks undergoing unique localised degradation patterns when exposed to sweetened environments. Consequently, the ability of both materials to return to clinically acceptable thresholds suggests that the initial discolouration was largely superficial and did not penetrate irreversibly into the core polymer matrix [4,8,24].
The physicochemical characteristics of composite materials are determined by each structural element and its harmony within the final matrix [7]. Both investigated materials are supra-nanospherical composites utilising monodisperse, 200 nm spherical silica–zirconia filler technology [5]. Recent systematic reviews confirm that these fillers represent a major structural advantage by allowing for a more homogenous distribution within the resin matrix and reducing the size of inter-filler spaces [23]. Ultimately, the ability of both composite materials to effectively release the stain suggests that the discolouration was primarily superficial [2,6,15].
Nonetheless, because the precise polymer cross-linking densities, silane-coupling efficiency, and dynamic water sorption rates of the tested specimens were not directly quantified in this study, the exact molecular behaviour of these specific matrices remains an area of experimental uncertainty.
Clinically, these findings highlight the vital distinction between statistical significance and clinical relevance. Although the materials exhibited statistically different initial kinetic behaviours, both supra-nanospherical materials achieved final residual colour changes well within the clinical acceptability range following routine maintenance. Under the conditions of this in vitro study, this suggests that they may be viable options for aesthetic restorations, as routine chairside repolishing appears to mitigate severe dietary discolouration without necessitating immediate restoration replacement.

4.2. Polishing Effect

The polishing procedure exerted a profound main effect across the entire clinical timeline. Under the experimental conditions of this study, the standard polishing method resulted in lower residual colour differences compared to the reduced method. It successfully reduced net colour shifts to levels that approached or fell below the perceptibility threshold (ΔE003 ≤ PT). In contrast, the reduced method resulted in residual discolouration that remained above the perceptibility threshold, though still within the clinically acceptable range (PT < ΔE003 ≤ AT). These findings align with several studies, which consistently suggest the clinical efficacy of the standard method [25].
A plausible mechanism for the higher colour stability of the standard method could involve the progression of abrasive grits. The sequential reduction in particle size (from coarse to extra-fine) could potentially allow for the systematic truncation and planarisation of surface asperities without gouging the resin matrix. Conversely, the reduced method utilises rigid, diamond-impregnated elastomeric wheels. One possible explanation is that these instruments generate highly localised mechanical forces that pluck or shear the spherical filler particles out of the softer polymer matrix, thereby hastening pigment accumulation [15]. Furthermore, the final step of the standard method involves an aluminium oxide polishing paste. It is possible that the ultra-fine abrasives in this paste effectively seal microscopic surface defects, creating a highly reflective surface barrier that resists subsequent pigment accumulation [4,25,26].
This difference in mechanical efficacy may be related to the abrasive geometry and the physical interaction between the polishing instruments and the composite microstructure. Regardless, because this in vitro study did not employ profilometric surface roughness (Ra) measurements, gloss analysis, or scanning electron microscopy (SEM), these mechanistic explanations remain subject to uncertainty. The exact micro-topography and the presence of suspected microscopic defects (such as filler plucking or micro-grooving) must be viewed as plausible interpretations rather than established mechanisms.
Clinically, these findings strongly emphasise the distinction between statistical differences and clinical relevance. While the two polishing systems produced statistically different outcomes, the reduced method still successfully brought the final residual colour shift well within clinically acceptable limits (ΔE00 ≤ 1.8). This represents a viable, time-saving option for routine restorations. Nevertheless, because the standard method achieved near-imperceptible residual discolouration (ΔE003 ≤ 0.8 in several groups), it remains the superior clinical choice for highly demanding anterior direct veneers where long-term aesthetic endurance is paramount.

4.3. Sugar Effect

A notable finding of this study was the distinct crossover behaviour induced by dietary sucrose. During the initial immersion phase, plain tea generated significantly higher discolouration than sucrose-sweetened tea. Despite this, following mechanical repolishing, this dynamic inverted completely. The present findings suggest that sugar may contribute to greater residual staining after repolishing.
These findings align with broader dental literature and recent systematic reviews evaluating composite colour stability, which consistently confirm that black tea is among the most potent chromogenic beverages due to its high concentration of chromogenic polyphenols [27]. Inevitably, the distinct role of sucrose in modulating this process has remained largely unexamined in broader meta-analyses.
To explain the lower initial staining in the sweetened tea groups, a plausible mechanism could involve the physical properties of the solvent. The addition of a high concentration of dietary sugar might increase the overall viscosity of the tea solution [28]. This may be due to the restricted kinetic mobility and downward diffusion of large tannin molecules, resulting in physical constraint by the high quantity of dietary sucrose. One possible mechanism is that their presence raised the dynamic viscosity of the aqueous medium. A thicker liquid might reduce the diffusion rate of the tannins into the microscopic pores of the resin matrix. Another contributing factor could involve competitive surface binding: it is hypothesised that the highly polar sucrose molecules may quickly form dense networks of hydrogen bonds across the composite surface, temporarily preventing tea pigments from adhering. Conversely, the finding that sweetened tea resulted in more persistent residual staining (ΔE003) points to a different interaction. This may be related to the formation of a sticky, high-viscosity sugar–polyphenol film on the composite surface. This organic film could act as a polymeric shield, trapping chromophores and facilitating deeper penetration or stronger chemical binding to the resin matrix over time. Additionally, some literature suggests that prolonged exposure to aqueous sugar solutions may relate to the plasticisation of the polymer matrix, which potentially increases free volume within the resin and allows pigments to diffuse deeper into the sub-surface layers, where superficial repolishing is less effective [20,29,30].
Nevertheless, considerable uncertainties remain regarding the precise physicochemical interactions at the composite–liquid interface. Because the specific molecular sizes of the pigment–sucrose complexes were not directly quantified in this study, and because this is an in vitro study, statements regarding hydrogen bonding, pigment diffusion, viscosity changes, and polymer plasticisation are presented strictly as plausible chemical hypotheses rather than directly observed facts.
Clinically, this may indicate that the regular consumption of sweetened beverages may accelerate the long-term aesthetic degradation of anterior direct veneers. Patients must be counselled that sweetened drinks may cause deep, permanent matrix staining that standard clinical polishing cannot fully resolve.

4.4. Interactions

The repeated-measures mixed ANOVA revealed significant two-way and three-way interactions across the experimental phases. This demonstrates that discolouration and reversibility are governed by a multi-factorial dynamic rather than by isolated variables. Additionally, it suggests that the multi-factor interactions are highly time-dependent.
These findings align with the previous literature, which implies that time plays an important role in discolouration. Colour stability is a complex process that involves multiple contributing factors [31].
The significant polishing vs. sugar interaction might offer a possibility of creating different surface topographies by utilising standard and reduced polishing methods [15]. Furthermore, the non-significant result of the composite vs. polishing interaction suggests that the superiority of the standard method is universally effective regardless of the composite material the clinician is polishing [5,15].
When exposed to sweetened tea, the two composites exhibited unique behavioural patterns. Because both materials share the same resin matrix and inorganic filler architecture, this variation cannot be attributed to differences in monomer composition. Instead, a plausible mechanism could be the differences in their proprietary curing technologies. One possible explanation is that photoinitiators might govern the rate of polymerisation and the ultimate cross-linking density of the polymer network [5].
The complex outcomes of the three-way interaction among the experimental variables demonstrate that the immediate volume of stain removal is a highly complex, simultaneous function. This process is potentially governed by the mechanical action of the polishing instruments, the specific cross-linking structure of the composite matrix, and the tangible adherence properties of the dietary intake [20,32,33].
However, because surface roughness (Ra), surface gloss, and the precise degree of conversion were not directly measured or imaged in this study, these multi-factor interactions remain proposed theoretical models.
Clinically, these interactions imply that the protective, smoothing benefit of a standard method is universally beneficial, as it effectively shields the composite from diverse dietary risks regardless of the selected composite material.

4.5. Correlation

The main findings regarding the correlation analysis of this study are a positive correlation between initial discolouration and the treatment phase and a negative mathematical discrepancy between the recovery success and early-stage aesthetic deterioration. This demonstrates that the total amount of stain removed during repolishing operates independently of the final aesthetic outcome.
This statistical disconnect is highly consistent with findings in dental materials experimental studies, which note that immediate aesthetic recovery does not always linearise with baseline disfigurement [34].
A plausible mechanism to explain the strong correlation between initial staining and the treatment shift involves the physical location of the early pigments. One possible explanation is that the majority of the early colouring agents might be held superficially on the outer layer of the composite. Because these pigments are loosely bound, they are highly susceptible to immediate mechanical shearing, meaning that the specimens with the heaviest early stain accumulation naturally experience the greatest absolute colour change during the repolishing phase [35]. Conversely, the complete lack of correlation with the final outcome may be related to deeper structural changes. It is highly probable that the permanent, residual discolouration is dictated by sub-surface pigment entrapment or localised matrix alterations, which operate under entirely different physical laws than superficial surface staining [25,32].
Despite this, our experimental design neither physically recorded the precise spatial depth of pigment penetration nor chemically analysed the border layer of the composite removed after repolishing. Accordingly, the hypothesised mechanical paths are inferences from statistics. Without direct physical tracking of the pigment migration front or quantitative determination of the exact thickness of the resin layer removed by the polishing equipment, the physical and chemical causes of this mathematical disconnect remain an area of experimental ambiguity.
From a clinical standpoint, this lack of association demonstrates that the final aesthetic achievement for a composite restoration is entirely unaffected by the extent to which it was stained initially. Even if black tea significantly exacerbates a severe early staining profile exceeding the acceptability threshold (ΔE00 > AT), it does not automatically condemn a restoration to irreversible failure. Because early discolouration severity does not predict final residual colour, bringing a heavily stained restoration back within clinically acceptable limits (ΔE00 ≤ AT) is achievable through appropriate mechanical maintenance.

4.6. Limitations

This study was conducted as an in vitro experimental comparison utilising standardised 3D-printed tooth guides. While this design allowed for a precise, controlled evaluation of colorimetric modifications across defined clinical timelines, several inherent limitations must be acknowledged to provide a balanced interpretation of the findings:
To maintain absolute consistency across specimen fabrication, use of the stamp guide, and application of handpiece pressure, all laboratory steps and spectrophotometric measurements were performed by a single trained investigator. While this approach successfully eliminated inter-operator variability, it inherently precluded examiner blinding during the colorimetric evaluation phase. However, all specimens were anonymised with numerical codes prior to spectrophotometric assessment to minimise operator bias.
This experiment could not fully replicate the complex, dynamic biochemistry of the human oral cavity. Crucially, the absence of natural human saliva is a primary limitation. Saliva plays a multi-faceted protective role, including the continuous formation of an acquired enamel pellicle that acts as a semi-permeable barrier against pigment adsorption, active bicarbonate buffering, and enzymatic clearance, leading to the natural dilution and washing away of both sucrose and tea chromophores.
The specimens did not undergo dynamic thermocycling or simulated toothbrushing prior to or during the staining process. Clinical restorations are subject to constant thermal stresses and physical abrasion from toothbrushing, which potentially degrade the superficial resin matrix, alter surface topography, and expose deeper filler layers to pigment penetration over time.
Furthermore, the protocol did not incorporate an oral biofilm. Under clinical in vivo conditions, the ingestion of dietary sucrose fuels acidogenic bacteria within dental plaque, creating localised lactic acid pools (acidolysis) that may chemically degrade and erode the composite resin matrix, thereby altering long-term colour stability.
Moreover, in this assessment, only two resin composites (PALFIQUE® LX5 and Estelite® Alpha) from the same manufacturer (Tokuyama Dental Corp., Tokyo, Japan) were evaluated. Although both materials are premier representatives of modern supra-nanospherical technology, evaluating composites from a single proprietary source means that these findings cannot be generalised to all supra-nanospherical composites on the market, nor to resin-based composites utilising fundamentally different monomer formulations, filler loadings, or curing architectures.
As visualised in the boxplot distributions (Figure 8, Figure 9 and Figure 10), certain experimental groups exhibited a broad dispersion of ΔE00 values. It is critical to note that to eliminate instrument degradation as a confounding factor, a new polishing instrument was utilised for every individual specimen (standard method) and for every five specimens (reduced method). Consequently, this data dispersion reflects the inherent structural variability of the composite resins rather than methodological error. It is possible that the mechanical action of polishing exposes the supra-nanospherical filler particles, creating subtle micro-topographical variations on a sample-by-sample basis. When exposed to a chromogenic medium, these microscopic surface differences potentially result in a broader range of pigment adsorption and subsequent colour change.
To build upon these findings, future research should incorporate dynamic thermocycling, toothbrushing simulation, longer ageing periods, and additional highly chromogenic beverages (such as coffee, red wine, and cola) to more accurately simulate dynamic oral challenges. Furthermore, future investigations should employ quantitative surface roughness measurements (Ra), gloss retention analysis, scanning electron microscopy (SEM), and multi-species biofilm models to physically verify the underlying degradation and staining mechanisms. Ultimately, in vivo clinical trials are recommended to fully validate the aesthetic endurance and stain reversibility of these supra-nanospherical materials under real-world clinical conditions.

5. Conclusions

Within the confines and constraints of this in vitro study, a highly dynamic interaction among material architecture, surface micro-topography, and the chemical characteristics of dietary chromogens determines the aesthetic lifecycle of dental resin composites, from initial discolouration to final repolishing. Based on the statistical and observational data, the following primary conclusions can be drawn:
  • Composite discolouration is a highly time-dependent process, and its optical degradation is not entirely linear. Under the evaluated conditions, the materials exhibited rapid initial stain accumulation followed by significant colour recovery after treatment, highlighting the dynamic nature of composite staining.
  • Both tested supra-nanospherical resin composites (PALFIQUE® LX5 and Estelite® Alpha) exhibited excellent overall aesthetic resilience. Despite undergoing severe initial discolouration (ΔE00 > AT), both materials successfully recovered to final residual colour differences well within clinically acceptable visual parameters (ΔE00 ≤ 1.8) following mechanical maintenance.
  • Under the experimental conditions of this study, the standard method resulted in lower residual colour differences, achieving near-imperceptible residual discolouration (ΔE00 ≤ PT). In comparison, the reduced method maintained within clinically acceptable limits (PT < ΔE00 ≤ AT).
  • The addition of dietary sucrose to black tea resulted in a distinct crossover behaviour: although sugar-sweetened tea produced lower initial stain uptake than plain tea, the present findings suggest that sugar may contribute to greater, more persistent residual discolouration after repolishing.
  • A complete lack of correlation was found between early staining severity and final aesthetic recovery. This indicates that a severe early-stage staining pattern does not automatically condemn a restoration to permanent failure.
Clinically, these findings highlight the importance of considering the persistent staining potential of sweetened beverages during the aesthetic maintenance of direct restorations. Ultimately, although the present findings support the use of a multi-step polishing protocol under controlled laboratory conditions, further well-designed clinical studies are needed before definitive clinical recommendations can be made.

Author Contributions

Conceptualization, H.W. and G.A.M.D.; methodology, H.W.; software, H.W.; validation, H.W.; formal analysis, H.W.; investigation, H.W.; resources, H.W., Hana Abdulsalam Muhammad Ali and Hadi Mohammad Ismail; data curation, H.W.; writing—original draft preparation, H.W.; writing—review and editing, H.W.; visualization, H.W.; supervision, G.A.M.D.; project administration, H.W.; funding acquisition, H.W. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

All data produced through this study are encompassed in this submitted manuscript.

Acknowledgments

We wish to express our sincere appreciation to Hana Abdulsalam Muhammad Ali at Foton Digital Dental Lab for generously granting access to his laboratory for the manufacture of the samples, which facilitated our work. We are also grateful for the support of Hadi Mohammad Ismail at his centre, City Smile Design Dental Centre, for graciously providing the VITA Easyshade V spectrophotometer and a studio room for precise measurements. Additionally, we express our deep gratitude to our colleague Hawre Mohammed Maarouf Ali for facilitating the entire photographic preparation of the study. Finally, this research would not have been possible without the patience and grounding presence of our families.

Conflicts of Interest

The authors declare no conflicts of interest.

Abbreviations

The following abbreviations are used in this manuscript:
ANOVAAnalysis of Variance
CIEDE2000Commission Internationale de l’Éclairage (International Commission on Illumination) Colour-Difference 2000
CAD/CAMComputer-Aided Design/Computer Additive Manufacturing
SLAStereolithography
DLPDigital Light Processing
ZrO2Zirconium Dioxide
SiO2Silicon Dioxide
Bis-GMABisphenol A-Glycidyl Methacrylate
TEGDMATriethylene Glycol Dimethacrylate
RPMRevolutions Per Minute
PSIPounds per Square Inch
DLP 3D printerDigital Light Processing Three-Dimensional Printer
LEDLight-Emitting Diode

References

  1. Smith, L.; Ali, M.; Agrissais, M.; Mulligan, S.; Koh, L.; Martin, N. A Comparative Life Cycle Assessment of Dental Restorative Materials. Dent. Mater. 2023, 39, 13–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Patel, M.; Lee, J.; Hayashi, M.; Kim, R.H.; Kim, M. Effect of Turmeric Staining and Bleaching Treatment on Color Stability and Surface Hardness of Different Dental Composite Resins. J. Compos. Sci. 2025, 9, 77. [Google Scholar] [CrossRef] [Scilit]
  3. Poggio, C.; Vialba, L.; Berardengo, A.; Federico, R.; Colombo, M.; Beltrami, R.; Scribante, A. Color Stability of New Esthetic Restorative Materials: A Spectrophotometric Analysis. J. Funct. Biomater. 2017, 8, 26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Kareem, A.S.A.; Abdel-Fattah, W.M.; El Gayar, M.I.L. Evaluation of Color Stability and Surface Roughness of Smart Monochromatic Resin Composite in Comparison to Universal Resin Composites after Immersion in Staining Solutions. BMC Oral Health 2025, 25, 1211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Sarıcı, T.; Dayı, B. Evaluation of the Effects of Different Polishing Systems on Surface Roughness and Surface Discoloration of Various Restorative Materials. BMC Oral Health 2025, 25, 978. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Eichenlaub, J.; Baran, K.; Urbański, K.; Robakowska, M.; Kalinowska, J.; Racka-Pilszak, B.; Kloskowski, A. In Search of the Perfect Composite Material—A Chemoinformatics Approach Towards the Easier Handling of Dental Materials. Int. J. Mol. Sci. 2025, 26, 8283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Podgórski, F.; Musyt, W.; Bociong, K.; Nijakowski, K. The Impact of Sports Drink Exposure on the Colour Stability of Restorative Materials: A Systematic Review. J. Compos. Sci. 2026, 10, 74. [Google Scholar] [CrossRef] [Scilit]
  8. Pyszka, I.; Bereźnicki, D.; Jędrzejewska, B. Light-Cured Dental Fillings Containing Quinoline and Quinoxaline Derivatives: The Influence of Sorption and Solubility on Color Change—Part III. Int. J. Mol. Sci. 2025, 26, 9537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Alkhadim, Y.K.; Hulbah, M.J.; Nassar, H.M. Color Shift, Color Stability, and Post-Polishing Surface Roughness of Esthetic Resin Composites. Materials 2020, 13, 1376. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Bahbishi, N.; Mzain, W.; Badeeb, B.; Nassar, H.M. Color Stability and Micro-Hardness of Bulk-Fill Composite Materials after Exposure to Common Beverages. Materials 2020, 13, 787. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Danila, A.I.; Breban-Schwarzkopf, D.; Daescu, E.; Olariu, I.; Dinu, S. Systematic Review of the Quality of Stereolithographic Three-Dimensionally Printed Materials for Provisional Dental Restorations. Materials 2025, 18, 721. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Šimunović, L.; Brenko, L.; Marić, A.J.; Meštrović, S.; Haramina, T. Rheology of Dental Photopolymers for SLA/DLP/MSLA 3D Printing. Polymers 2025, 17, 2706. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Bolat, Ç.; Salmaz, S. An Investigation on the Wear Properties of the Photocurable Components Produced by Additive Manufacturing for Dentistry Applications: Combined Influences of UV Exposure Time, Building Direction, and Sliding Loads. Polym. Eng. Sci. 2024, 64, 5940–5958. [Google Scholar] [CrossRef] [Scilit]
  14. Moldovan, M.; Dudea, D.; Cuc, S.; Sarosi, C.; Prodan, D.; Petean, I.; Furtos, G.; Ionescu, A.; Ilie, N. Chemical and Structural Assessment of New Dental Composites with Graphene Exposed to Staining Agents. J. Funct. Biomater. 2023, 14, 163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Freitas, F.; Pinheiro de Melo, T.; Delgado, A.H.; Monteiro, P.; Rua, J.; Proença, L.; Caldeira, J.; Mano Azul, A.; Mendes, J.J. Varying the Polishing Protocol Influences the Color Stability and Surface Roughness of Bulk-Fill Resin-Based Composites. J. Funct. Biomater. 2021, 12, 1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Dennis, T.; Zoltie, T.; Wood, D.; Altaie, A. Reduced-Step Composite Polishing Systems—A New Gold Standard? J. Dent. 2021, 112, 103769. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Dalloo, G.A.M.; Faraj, B.M.; Al-Zahawi, A.R. Impact of Bleaching before or after Veneer Preparation on Color Masking Ability of Laminate Veneers: An In Vitro Study. BioMed Res. Int. 2021, 2021, 6611173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Faris, T.M.; Abdulrahim, R.H.; Mahmood, M.A.; Mhammed Dalloo, G.A.; Gul, S.S. In Vitro Evaluation of Dental Color Stability Using Various Aesthetic Restorative Materials after Immersion in Different Drinks. BMC Oral Health 2023, 23, 49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Mousdraka, M.G.; Gerasimidou, O.; Nikolaidis, A.K.; Gogos, C.; Koulaouzidou, E.A. Evaluation of Color Stability of UDMA-Based Dental Composite Resins After Exposure to Conventional Cigarette and Aerosol Tobacco Heating System. J. Compos. Sci. 2025, 9, 352. [Google Scholar] [CrossRef] [Scilit]
  20. Nilay, B.; Pirpir, Y.H.Y.; Harorlı, O. Do Sugary Drinks Color Bulk-Fill Composİte More? Akdeniz Diş Hekimliği Dergisi 2025, 4, 76–82. [Google Scholar] [CrossRef] [Scilit]
  21. Qaraghuli, A.M.; Signore, A.; Benedicenti, S.; Halawani, M.T.E.; Solimei, L. Comparison and Effect of Common Beverages on Color Stability of Different Esthetic Restorative Materials: An In Vitro Study. J. Contemp. Dent. Pract. 2023, 23, 1085–1090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Sajini, S.I.; Mushayt, A.B.; Almutairi, T.A.; Abuljadayel, R. Color Stability of Bioactive Restorative Materials After Immersion in Various Media. J. Int. Soc. Prev. Community Dent. 2022, 12, 418. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Abd-Elfattah, H.Y.; Elawsya, M.E.; ElEmbaby, A.E. Impact of Immersion in Different Storage Media on Color Stability, Surface Roughness, and Surface Microhardness of Different Flowable Resin Composites: Literature Review. Egypt. Dent. J. 2025, 71, 3613–3634. [Google Scholar] [CrossRef] [Scilit]
  24. Barszczewska-Rybarek, I.M.; Chrószcz, M.W.; Chladek, G. Physicochemical and Mechanical Properties of Bis-GMA/TEGDMA Dental Composite Resins Enriched with Quaternary Ammonium Polyethylenimine Nanoparticles. Materials 2021, 14, 2037. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Haberal, M.; Türkoğlu, E.; Bayraktar, Y. Effect of Repolishing on the Color Stability of a Supra-Nano Spherical Filled Composite Resin: An in Vitro Study. J. Dent. Res. Dent. Clin. Dent. Prospects 2025, 19, 115–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Gawriołek, M.; Varma, N.; Hernik, A.; Eliasz, W.; Strykowska, M.; Paszyńska, E.; Czarnecka, B.; Sikorski, M. Investigating the Mechanisms of Discoloration in Modern Dental Materials: A Comprehensive Characterization Approach. J. Funct. Biomater. 2024, 15, 246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Alenezi, A.Y.; AlEyada, A.M.; Aldhafiri, Y.H.; Alsubaie, M.S.; Alshahrani, M.S.; Shenoy, M. Color Stability of Tooth-Colored Restorative Materials After Exposure to Arabic Coffee and Black Tea: A Systematic Review. Cureus 2025, 17, e92294. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Zeng, L.; Walker, A.R.; Calderon, P.d.S.; Xia, X.; Ren, F.; Esquivel-Upshaw, J.F. The Effect of Amino Sugars on the Composition and Metabolism of a Microcosm Biofilm and the Cariogenic Potential against Teeth and Dental Materials. J. Funct. Biomater. 2022, 13, 223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Al-Shami, A.M.; Alshami, M.A.; Al-Kholani, A.I.; Al-Sayaghi, A.-A.M. Color Stability of Nanohybrid and Microhybrid Composites after Immersion in Common Coloring Beverages at Different Times: A Laboratory Study. BDJ Open 2023, 9, 39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Al-Dulaijan, Y.A.; AlGhamdi, M.A.; Azmy, E.; Al-Kholy, M.R.Z.; Almulhim, K.S.; Helal, M.A. Color Stability of Nanoparticles-Modified Dental Resin-Based Composites. Appl. Sci. 2023, 13, 3870. [Google Scholar] [CrossRef] [Scilit]
  31. Mohsen, M.; Pergolini, D.; Nistor, E.B.; Habilaj, S.; Migliau, G.; Marini Grassetti, F.; Polimeni, A.; Palaia, G. Color Stability of Single-Shade Resin Composites: A Systematic Review of In Vitro Studies and Clinical Implications. Dent. J. 2026, 14, 293. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Gawriołek, M.; Gawriołek, K.; Eliasz, W.; Czarnecka, B.; Paszynska, E.; Sikorski, M. How Does the Color of Restorative Material Change during Exposure to Dietary Liquids Due to the Acquisition of a Discolored Layer? Coatings 2020, 10, 866. [Google Scholar] [CrossRef] [Scilit]
  33. Marufu, C.; Kisumbi, B.K.; Osiro, O.A.; Otieno, F.O. Effect of Finishing Protocols and Staining Solutions on Color Stability of Dental Resin Composites. Clin. Exp. Dent. Res. 2022, 8, 561–570. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Şahin, H.C.; Korkut, B. Color Adjustment of Single-Shade Composites Following Staining, Repolishing, and Bleaching Procedures. BMC Oral Health 2025, 25, 248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Karakaş, S.N.; Batmaz, S.G.; Çiftçi, V.; Küden, C. Experimental Study of Polishing Systems on Surface Roughness and Color Stability of Novel Bulk-Fill Composite Resins. BMC Oral Health 2025, 25, 74. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. 3D-printing of study samples: (a) software design of an ideal maxillary right central incisor prepared for a direct veneer; (b) verification of dimensions to prevent discrepancies; (c) 3D-printed dental resin sample; (d) prepared tooth displaying a standardised configuration; (e) construction of a clear guide; (f) printed clear guide used as a stamp to replicate the anatomical contours of the ideal veneer restoration; and (g) final printed and numbered samples.
Jcs 10 00398 g001
Scheme 1. Allocation of printed samples into experimental groups. The specimens were randomly assigned to their respective groups and subsequently numbered.
Jcs 10 00398 sch001
Figure 2. Supra-nanospherical composite filling materials used for the samples: (a) Tokuyama PALFIQUE® LX5, used for Groups 1–4; (b) Tokuyama Estelite® Alpha, used for Groups 5–8; and (c) samples restored with direct veneers and ready for polishing.
Jcs 10 00398 g002
Figure 3. Polishing systems: (a) the standard method used for Groups 1, 2, 5, and 6; (b) the reduced method used for Groups 3, 4, 7, and 8.
Jcs 10 00398 g003
Figure 4. The experimental sample groups were categorised as follows: Groups 1 and 2 (PALFIQUE® LX5 with the standard method); Groups 3 and 4 (PALFIQUE® LX5 with the reduced method); Groups 5 and 6 (Estelite® Alpha with the standard method); and Groups 7 and 8 (Estelite® Alpha with the reduced method).
Jcs 10 00398 g004
Figure 5. Samples stored in the immersion solution, numbered according to group and sample number.
Jcs 10 00398 g005
Figure 6. Samples after 28 days: (a) after immersion and (b) after repolishing.
Jcs 10 00398 g006
Figure 7. Bar chart illustrating the colour shifts among the experimental groups at initial discolouration, after polishing and at final recovery: (1) PALFIQUE® LX5, standard polishing, plain tea; (2) PALFIQUE® LX5, standard polishing, sugar; (3) PALFIQUE® LX5, reduced polishing, plain tea; (4) PALFIQUE® LX5, reduced polishing, sugar; (5) Estelite® Alpha, standard polishing, plain tea; (6) Estelite® Alpha, standard polishing, sugar; (7) Estelite® Alpha, reduced polishing, plain tea; and (8) Estelite® Alpha, reduced polishing, sugar.
Jcs 10 00398 g007
Figure 8. Box plot presenting the initial discolouration of the samples (ΔE001).
Jcs 10 00398 g008
Figure 9. Box plot presenting the repolishing outcomes of the samples (ΔE002).
Jcs 10 00398 g009
Figure 10. Boxplot presenting the final recovery outcomes of the samples (ΔE003).
Jcs 10 00398 g010
Figure 11. A line graph showing different colour stability between: (a) Two nanospherical composites (PALFIQUE® LX5 and Estelite® Alpha); (b) Standard and reduced polishing systems; and (c) Plain tea and tea with sugar, through three intervals: initial staining, treatment, and recovery phase.
Jcs 10 00398 g011
Table 1. Technical 3D printing parameters and production constants.
ParametersVeneer-Prepared Tooth ModelsStandardising Guide Stamp
3D Printer ModelSprintRay Pro 2 (SprintRay Inc., Los Angeles, CA, USA)SprintRay Pro 2 (SprintRay Inc., Los Angeles, CA, USA)
Technology TypeDigital Light Processing (DLP)Digital Light Processing (DLP)
Light Source Wavelength385 nm385 nm
MaterialDental Model, Dune shade (SprintRay Inc., Los Angeles, CA, USA)MAZIC D SG (Vericom Co., Ltd., Chuncheon, Gangwon-do, Republic of Korea)
Material ClassificationDental Model Photopolymer ResinClear Surgical Guide Photopolymer Resin
CompositionUDMA/methacrylated oligomer baseUDMA oligomer matrix (~50–70 wt%)
Reactive methacrylate diluentsMethacrylic monomers (~20–40 wt%)
Phosphine oxide initiatorPhosphine oxide initiator (~1–5 wt%)
Opaque pigmentsUV stabilisers
Batch Number2025092602SG640100
Layer Thickness50 μm100 μm
Build Orientation45° relative to the platform0° (flat relative to the platform)
Post-Curing UnitSprintRay ProCure 2 (SprintRay Inc., Los Angeles, CA, USA)SprintRay ProCure 2 (SprintRay Inc., Los Angeles, CA, USA)
Post-Curing Time5 min10 min
Table 2. Chemical composition and specifications of tested supra-nanospherical resin composites.
Composite
Material
ManufacturerShadeMonomer
Matrix
Inorganic Filler
Composition and Size
Filler LoadingBatch Number
PALFIQUE® LX5Tokuyama Dental Corp., Tokyo,
Japan
A1Bis-GMA, TEGDMAMonodisperse spherical silica–zirconia
(200 nm/0.2 μm)
82 wt%
(71 vol%)
410E65
Estelite® AlphaTokuyama Dental Corp., Tokyo,
Japan
A1Bis-GMA, TEGDMAMonodisperse spherical silica–zirconia
(200 nm/0.2 μm)
82 wt%
(71 vol%)
227E65
Table 3. Polishing systems evaluated in this study.
Polishing ProtocolArmamentariumManufacturerComposition/TypeHandpiece RPMBatch Number
Standard MethodEVE Flexi-D DiscsEVE Ernst Vetter GmbH, Pforzheim, GermanyFlexible polyurethane backing with aluminium oxide abrasive grids (blue, red, yellow and white)10,000502256
Prisma GlossDentsply Sirona, York, PA, USAFine-grit aluminium oxide polishing paste500000121778
Enhance FoamDentsply Sirona, York, PA, USAPolyurethane foam polishing cups500000121734
Reduced MethodEVE Diacomp Wheels
(Diacomp Plus)
EVE Ernst Vetter GmbH, Pforzheim, GermanyDiamond-impregnated silicone polishing wheels (pink and grey)10,000533636
Table 4. Clinical interpretation thresholds for CIEDE2000 (ΔE00) colour differences.
Threshold CategoryΔE00 RangeClinical Interpretation
ImperceptibleΔE00 ≤ 0.8Colour difference cannot be detected by the human eye (50% PT)
Perceptible/Acceptable0.8 < ΔE00 ≤ 1.8Noticeable difference, but clinically acceptable (50% AT)
Clinically UnacceptableΔE00 > 1.8Severe colour shift requiring clinical intervention or replacement
PT = perceptibility threshold, AT = acceptability threshold.
Table 5. Mean colour difference (ΔE00) values, standard deviations, and 95% confidence intervals for direct veneer samples across all experimental groups.
GroupComposite TypePolishing
System
MediumNo∆E001 ± SD
[95% CI]
∆E002 ± SD
[95% CI]
∆E003 ± SD
[95% CI]
1PALFIQUE® LX5Standard methodPlain tea104.872 ± 1.850
[3.549, 6.195]
4.512 ± 1.745
[3.263, 5.760]
1.004 ± 0.568
[0.598, 1.410]
2PALFIQUE® LX5Standard methodTea + sugar105.407 ± 1.836
[4.093, 6.720]
5.241 ± 1.095
[4.457, 6.024]
1.410 ± 0.836
[0.812, 2.001]
3PALFIQUE® LX5Reduced methodPlain tea107.037 ± 0.798
[6.467, 7.601]
6.714 ± 1.134
[5.903, 7.525]
1.126 ± 0.531
[0.746, 1.505]
4PALFIQUE® LX5Reduced methodTea + sugar105.427 ± 1.765
[4.165, 6.690]
5.416 ± 1.426
[4.396, 6.437]
1.136 ± 0.367
[0.874, 1.398]
5Estelite® AlphaStandard methodPlain tea106.603 ± 0.965
[5.913, 7.294]
6.589 ± 1.055
[5.834, 7.343]
0.423 ± 0.176
[0.298, 0.549]
6Estelite® AlphaStandard methodTea + sugar105.134 ± 0.973
[4.438, 5.830]
5.190 ± 0.917
[4.534, 5.846]
0.403 ± 0.225
[0.242, 0.564]
7Estelite® AlphaReduced methodPlain tea107.237 ± 1.307
[6.302, 8.171]
6.617 ± 1.072
[5.850, 7.384]
1.012 ± 0.313
[0.788, 1.236]
8Estelite® AlphaReduced methodTea + sugar105.096 ± 1.474
[4.041, 6.150]
4.877 ± 1.473
[3.824, 5.930]
0.838 ± 0.393
[0.557, 1.118]
Total 805.852 ± 1.6305.644 ± 1.4600.919 ± 0.558
SD: standard deviation, CI: 95% confidence interval.
Table 6. Summary of the three-way repeated-measures mixed ANOVA.
Source of VariationsdfFp-Valueηp2Effect Size Power
Within-Subjects Effects
Time1.339896.587<0.001 **0.926Extremely Large
Time * Composite1.3396.7630.006 *0.086Medium/Large
Time * Polishing1.3391.6850.1980.023Small
Time * Sugar1.33912.141<0.001 **0.144Large
Time * Composite * Polishing1.3397.0570.005 *0.089Medium/Large
Time * Composite * Sugar1.3392.2630.1270.030Small
Time * Polishing * Sugar1.3392.5920.1000.035Small
Time * Composite * Polishing * Sugar1.3391.0950.3170.015Small
Between-Subjects Effects
Composite10.0870.7690.001Neglectable
Polishing15.5570.021 *0.072Medium
Sugar111.242<0.001 **0.135Large
Composite * Polishing11.5940.2110.022Small
Composite * Sugar15.5000.022 *0.071Medium
Polishing * Sugar15.5370.021 *0.071Medium
Composite * Polishing * Sugar11.9460.1670.026Small
df: degree of freedom, ηp2: partial eta-squared [effect size ηp2 ≈ 0.01 (small); ηp2 ≈ 0.06 (medium); ηp2 ≈ 0.14 (large)], * p-value < 0.05, ** p-value < 0.001.
Table 7. Bonferroni-adjusted post hoc pairwise comparisons for the main effect of time on colour difference (ΔE00).
Time ComparisonMean Difference (I–J)Standard Errorp-Value95% Confidence Interval
ΔE001 vs. ΔE0020.2070.0730.017 *[0.029, 0.385]
ΔE001 vs. ΔE0034.9330.157<0.001 **[4.547, 5.318]
ΔE002 vs. ΔE0034.7250.149<0.001 **[4.361, 5.090]
ΔE001, ΔE002, and ΔE003 represent the three repeated measurement time points. A positive mean difference indicates that the first time point (I) exhibited a higher colour change value than the second time point (J). An asterisk indicates statistical significance: * p-value < 0.05, ** p-value < 0.001.
Table 8. Pearson correlation analysis.
Pearson Correlation AnalysisΔE001ΔE002ΔE003
ΔE001Pearson Correlation10.916 **0.147
Sig. (2-tailed) 0.0000.195
ΔE002Pearson Correlation0.916 **10.001
Sig. (2-tailed)0.000 0.995
ΔE003Pearson Correlation0.1470.0011
Sig. (2-tailed)0.1950.995
** Correlation is significant at the 0.01 level (2-tailed).
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.