Article

Distribution of Mother-to-Child Transmitted (MTCT) Infections and Socioeconomic Vulnerability Within the Gran Chaco Region


by
Carla Rodríguez González
1,2,*,
Susana Ávila
3,
Karina Cardone
3,
Mariana Fernández
3,
Favio Crudo
3,
Verónica Andreo
1,2 and
M. Victoria Periago
2,3
1
The Instituto de Altos Estudios Espaciales Mario Gulich (CONAE-UNC), Cordoba X5186AAE, Argentina
2
National Scientific and Technical Research Council (CONICET), Buenos Aires C1033AAJ, Argentina
3
Fundación Mundo Sano, Buenos Aires C1053ABK, Argentina
*
Author to whom correspondence should be addressed.
Trop. Med. Infect. Dis. 2026, 11(7), 188; https://doi.org/10.3390/tropicalmed11070188
Submission received: 27 May 2026 / Revised: 1 July 2026 / Accepted: 6 July 2026 / Published: 8 July 2026
(This article belongs to the Section Neglected and Emerging Tropical Diseases)

Abstract

Mother-to-child transmission (MTCT) of infectious diseases remains a public health challenge in socially vulnerable regions with limited healthcare access. This study assessed the epidemiological situation, spatial distribution, and socioeconomic context of MTCT infections—Chagas disease (ChD), syphilis, HIV, and hepatitis B (HB)—in the Gran Chaco region (Argentina–Paraguay), 2018–2024. Epidemiological data from 2877 patients enrolled in an MTCT Plus programme were analysed, alongside socioeconomic variables and spatio-temporal cluster analysis using SaTScan software. Maternal seroprevalence of ChD was 4.1%, the highest among the infections evaluated. Syphilis prevalence was 0.8%, while no HIV or HBV infections were detected among screened pregnant women. Two statistically significant spatiotemporal clusters of maternal Trypanosoma cruzi seropositivity were identified: a household-level cluster in 2018 and a regional cluster during 2019–2021. The highest prevalence of maternal ChD seropositivity was observed in census tracts with greater socioeconomic vulnerability, although this spatial overlap was assessed descriptively. These findings highlight the effectiveness of integrated maternal–child health services in ensuring coverage, timely diagnosis, and treatment in vulnerable populations. The identified spatial patterns provide evidence to support targeted surveillance and coordinated binational public health strategies in border regions affected by persistent social inequalities.

1. Author Summary

In this study, we investigated the distribution of infections with potential for MTCT—including Chagas disease, HIV, syphilis, and hepatitis B—in the Gran Chaco region of Argentina and Paraguay by combining epidemiological information, spatial analyses, and socioeconomic indicators.
Maternal seroprevalence of ChD was the highest among the infections evaluated, and two spatiotemporal clusters of maternal T. cruzi seropositivity were identified. Areas with higher maternal seroprevalence also exhibited greater socioeconomic vulnerability, although this relationship was assessed descriptively. Our findings demonstrate the value of integrated maternal and child healthcare programmes for achieving broad screening coverage, follow-up, and timely treatment, while providing evidence to guide surveillance and coordinated cross-border public health strategies in underserved populations.

2. Introduction

Mother-to-child transmission (MTCT) of HIV, syphilis, Hepatitis B virus (HBV), and Chagas disease (ChD) remains a significant public health concern in Latin America and the Caribbean (LAC), particularly in resource-limited settings where these diseases substantially contribute to morbidity and mortality [1,2]. According to the latest Pan American Health Organization’s (PAHO) reports for the region, approximately 2100 children per year are born with or acquire HIV from their mothers, 22,400 are infected with syphilis, 9000 are born with T. cruzi, the causative agent of ChD, and 6000 contract HBV infection [3]. Early detection of these infections during pregnancy enables effective therapeutic interventions for mothers and children. If left undiagnosed and untreated, they can lead to severe complications, including miscarriage, congenital and neurological disorders, cardiac conditions, and, in some cases, death [4].
Over the past two decades, the World Health Organization (WHO) and PAHO have led efforts to combat these diseases, initially focusing on HIV and syphilis and later expanding to include HB and ChD under the Framework for the Elimination of Mother-to-Child Transmission (EMTCT Plus) [5,6]. This initiative underscores the importance of a comprehensive approach to maternal and child health, ensuring timely access to diagnosis and treatment during pregnancy while promoting gender equity, empowerment, and the protection of human rights, including maternal health.
Despite the progress achieved through implementing the EMTCT Plus programme, reaching regional elimination targets remains challenging. Disparities in access to healthcare and other social determinants of health continue to hinder progress [7,8]. Although eight countries in the Americas have obtained WHO certification for the dual elimination of congenital HIV and syphilis, progress remains uneven. The regional MTCT rate of HIV stands at approximately 10%, far exceeding the target of 2%, while the incidence of congenital syphilis is 2 per 100,000 live births, surpassing the goal of 0.5. Moreover, ChD screening among pregnant women varies widely, with prevalence rates ranging from 7% to 55% [9,10].
The persistence of MTCT is closely linked to structural deficiencies in health systems, especially in the coverage and quality of prenatal care. Numerous studies have shown that delays in diagnosis, insufficient clinical follow-up, and inadequate treatment significantly increase the risk of vertical transmission [11,12]. Moreover, individual and social factors, such as maternal education level, employment status, ethnicity, and access to timely and adequate prenatal care, are known to compound this risk [13,14,15]. Generating context-sensitive evidence is key for guiding health authorities in designing and implementing more effective, equitable, and sustainable interventions.
The American Gran Chaco, particularly the Tri-Border region between Argentina, Bolivia, and Paraguay, is one of several areas where social and environmental determinants heavily influence health outcomes. It is marked by chronic poverty and a high proportion of indigenous and rural populations facing deep structural inequities. Factors such as food insecurity, poor access to clean water and sanitation, and precarious housing conditions all contribute to elevated maternal and infant morbidity and mortality [16,17].
Identifying geographical patterns and epidemiological trends is essential for guiding more effective and targeted public health strategies, enabling the optimisation of resources and the implementation of interventions directed at the most vulnerable populations [18,19]. Understanding the distribution of these infections not only strengthens the local health system but also facilitates evidence-based decision-making to advance the elimination of MTCT in contexts of high inequality and structural challenges. Here, we describe the spatial and temporal distribution of ChD, syphilis, HIV, and HBV infections in pregnant women in a region of the Gran Chaco, in relation to socioeconomic deprivation.

3. Methods

3.1. Study Area

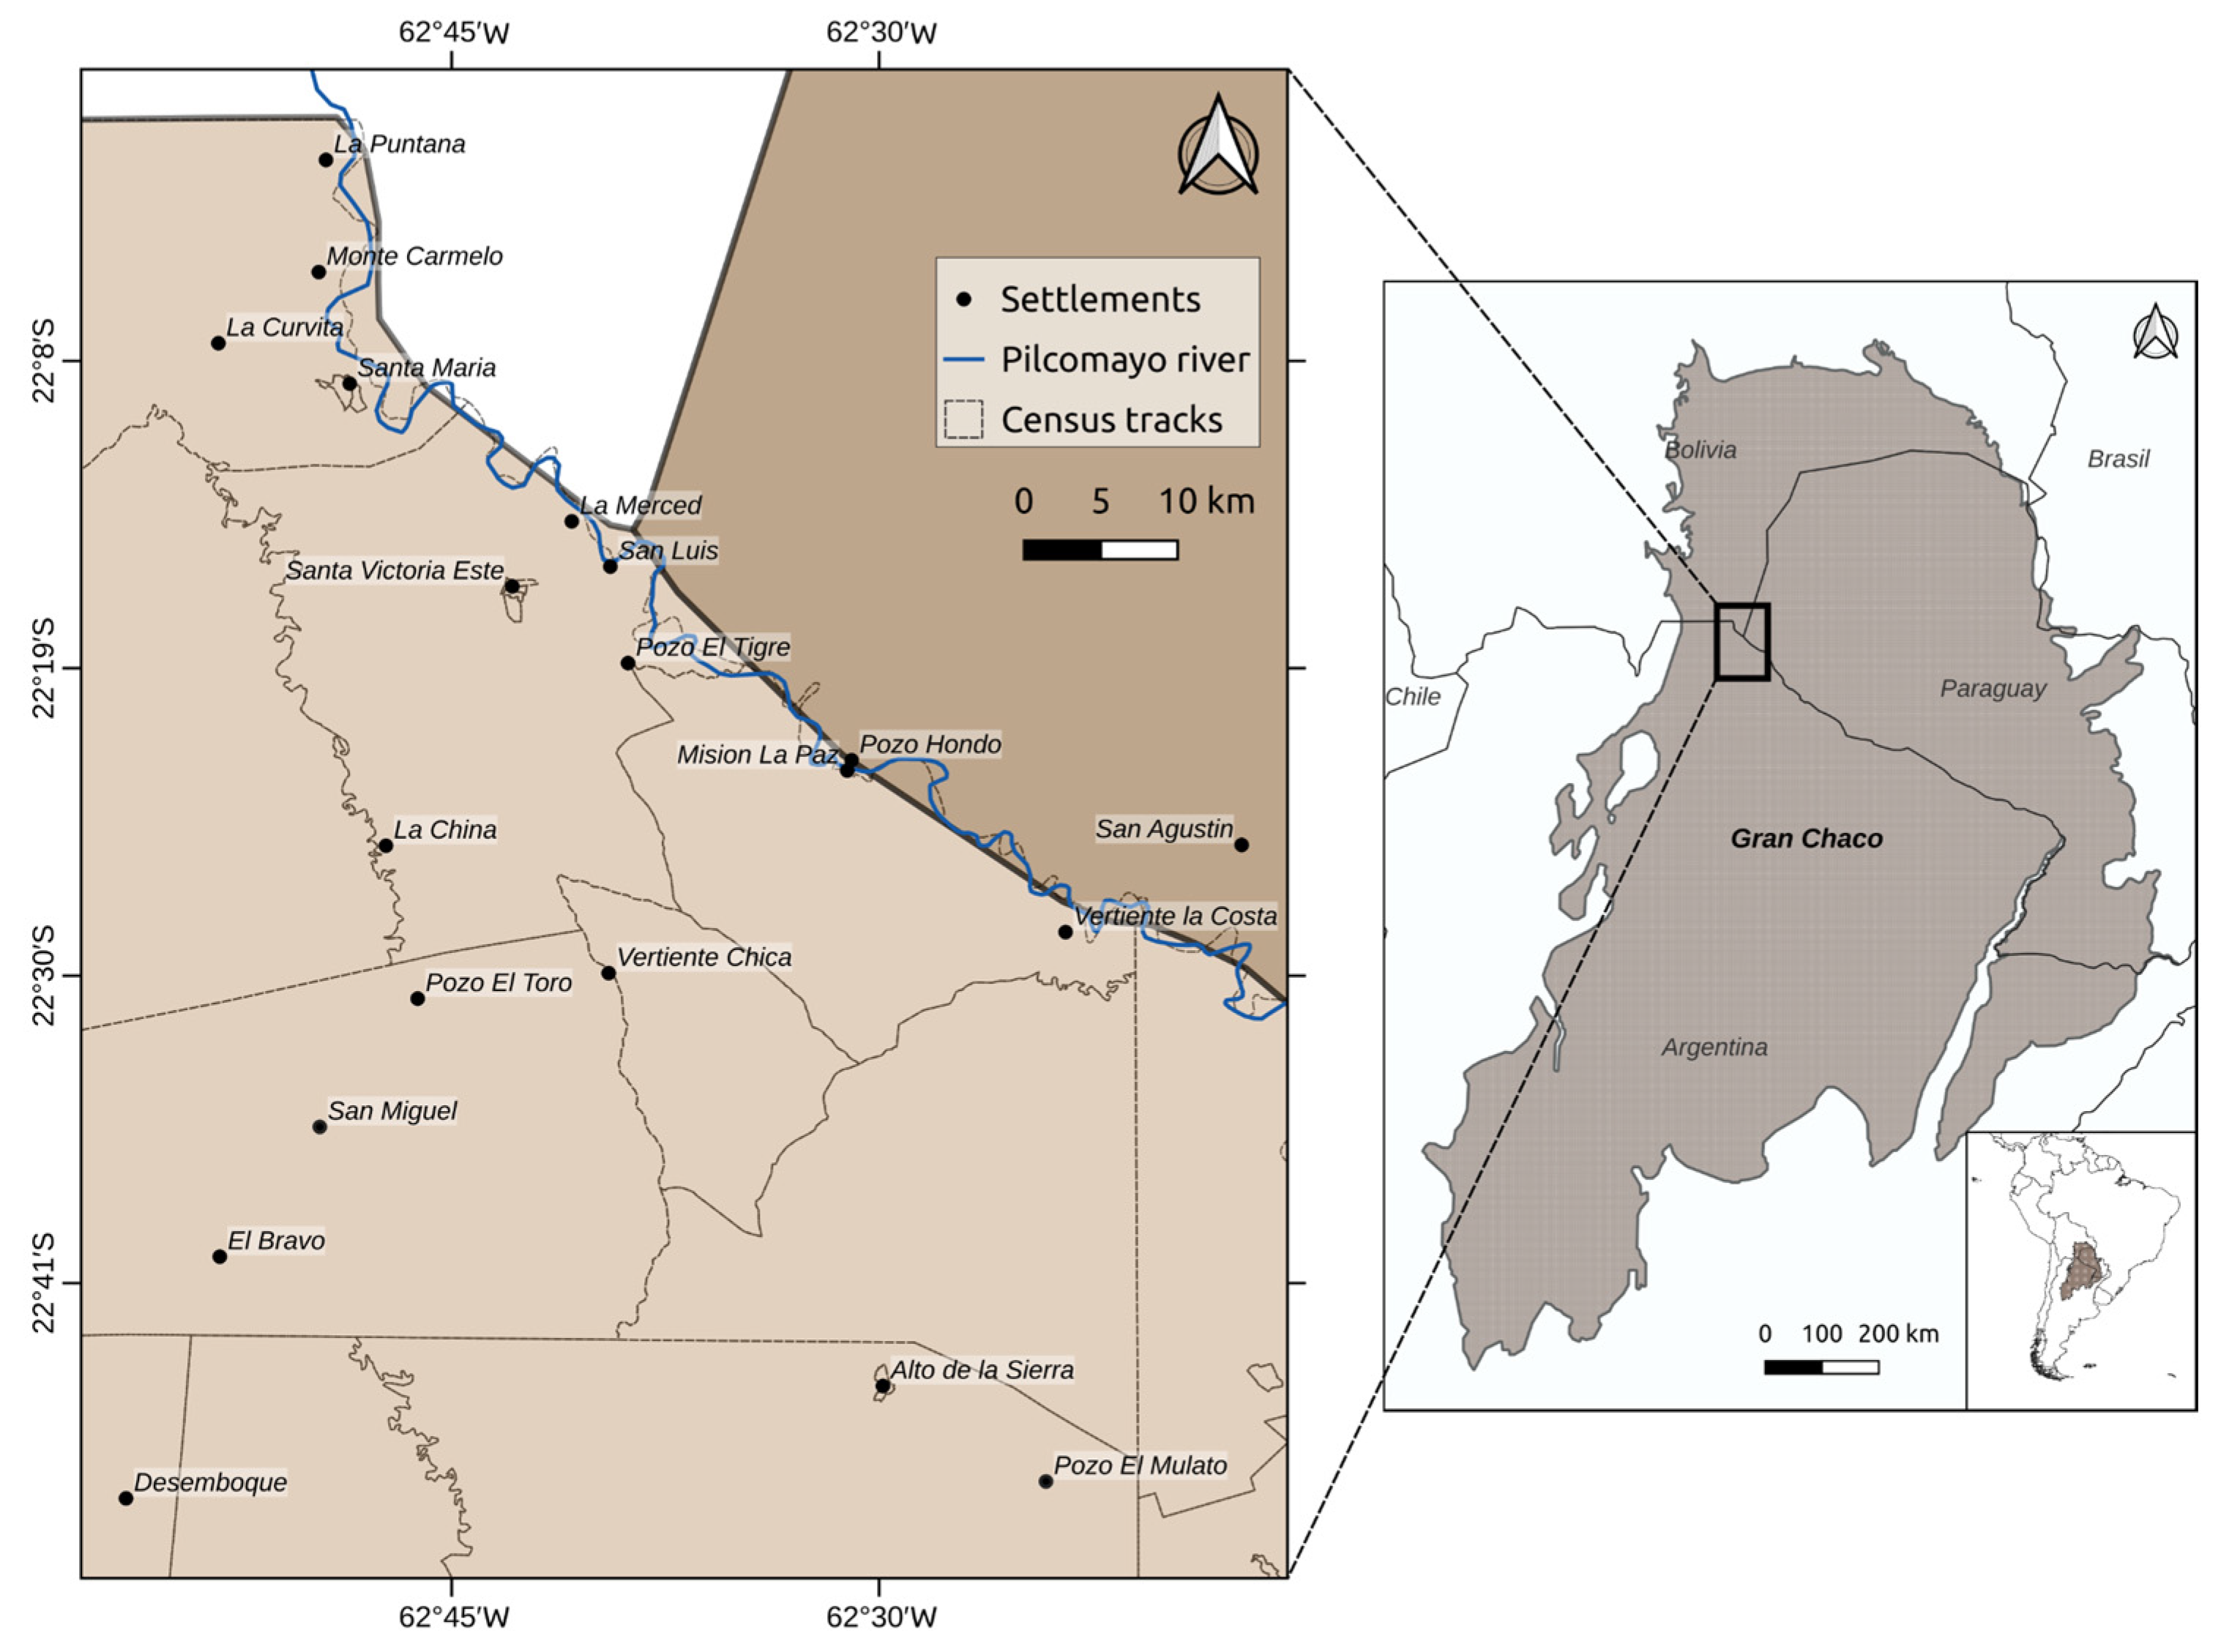
The study area encompassed a transboundary Gran Chaco region, including Santa Victoria Este and Alto la Sierra in Argentina, D’Orbigny in Bolivia, and Pozo Hondo and San Agustín in Paraguay (Figure 1). This region, with an approximate area of 7600 km2 and an estimated population of 13,500 inhabitants according to the most recent census data [20], is characterised as a cultural mosaic of indigenous communities that have historically converged there due to migratory processes. The population distribution is highly heterogeneous and is largely determined by water availability and frequent overflows of the Pilcomayo River that pose recurrent challenges to local communities.
The region has a subtropical climate, with a dry season from April to December and a rainy season during the remaining months. Annual precipitation varies between 500 and 700 mm. Temperatures vary widely, often exceeding 40 °C in summer, while in the south and southwest, winter temperatures can drop below 0 °C [16]. The combination of flooding and prolonged droughts further exacerbates environmental and socio-economic vulnerabilities. Additionally, the predominant xerophytic forest vegetation has been largely replaced by agriculture and livestock farming, resulting in landscape transformation and competition for resources [16].

3.2. Data

3.2.1. Epidemiological Data

The epidemiological data were collected between 2018 and 2024 in the framework of the EMTCT Plus initiative, implemented by two non-governmental organizations (NGOs), Fundación Mundo Sano (FMS) and Asociación para el Desarrollo Sanitario Regional (ADESAR), in collaboration with local, regional, and national health authorities. This initiative has been implemented since 2018 to support the elimination of MTCT of HIV, syphilis, HB, and ChD in vulnerable populations across the Tri-Border region [21,22,23]. A specialised team provided antenatal care during periodic field visits conducted approximately every 60 days. Each visit consisted of an intensive five-day intervention period, during which the team performed antenatal care activities, supported by local healthcare professionals and health system actors who ensured continuity of care between visits. Data collection was conducted at health posts in seven localities within the municipality of Santa Victoria Este and the locality of Alto la Sierra, Rivadavia Department, Salta Province (Argentina), as well as at two health posts in the localities of Pozo Hondo and San Agustín, Boquerón Department (Paraguay). Demographic information, including age, sex, ethnicity, and household distribution, was recorded for all pregnant, postpartum, and breastfeeding women. Additionally, local medical records were collected to document the follow-up and management of HIV, syphilis, HBV, and ChD in the aforementioned groups, as well as in children, siblings, and/or partners of pregnant women enrolled in the implementation.
The diagnosis and clinical management of HIV, syphilis, HBV, and T. cruzi infection followed the national diagnostic algorithms recommended by the Argentine Ministry of Health [24]. Maternal HIV, syphilis, and HBV infections were diagnosed using the recommended serological algorithms, including HBsAg detection for HBV. Maternal T. cruzi infection was confirmed by conventional serology using two assays based on different analytical principles. Congenital ChD was diagnosed according to the national algorithm using parasitological methods and/or real-time PCR during the neonatal period, or by conventional serology after 10 months of age when early tests were negative.
Details on the study setting and population demographics have been published elsewhere [22].

3.2.2. Case Distribution

Confirmed cases were georeferenced at the household level using a GPS device (Garmin eTrex 32x; Garmin Ltd., Olathe, KS, USA). Geographic coordinates were collected using the Universal Transverse Mercator (UTM) projection, zone 21S. These operations covered over 15 settlements within the study area and involved collaboration with nursing staff, community health agents, and local community members.

3.2.3. Socioeconomic Data

Socioeconomic data were obtained from the most recent population census in Argentina and Paraguay (2022) [20,25] and correspond to the Unmet Basic Needs (UBN) index, which identifies households experiencing deprivation in at least one of the following categories: housing conditions (precarious or non-residential dwellings), sanitary conditions (lack of a toilet), overcrowding (more than three persons per room), school attendance (at least one child aged 6–12 not attending school), and subsistence capacity (high dependency ratio and low educational attainment of the household head). In addition to these categories, we also considered specific variables related to housing conditions, including households without access to piped water for drinking and cooking, households without a type 1 roof covering (membrane, tile, slab, or shingle), and households without a type 1 floor covering (ceramic, tile, mosaic, marble, wood, or carpet).

3.3. Data Processing

3.3.1. Socioeconomic Analysis

To explore the spatial relationship between infection distribution and socioeconomic conditions, thematic maps were generated at the census tract level for the UBN index and its individual components. The spatial distribution of maternal T. cruzi seropositivity and syphilis cases was then descriptively compared with these socioeconomic indicators to identify areas of potential spatial co-occurrence between infection and social deprivation. No formal statistical analyses were performed; therefore, this component of the study was intended as a descriptive spatial assessment rather than an inferential analysis of association.

3.3.2. Spatio-Temporal Clustering Patterns

Clustering patterns of cases for the four infections studied were analysed using a discrete Poisson space-time scan model implemented in the SaTScan software v10.3 (Information Management Services, Inc., Rockville, MD, USA) [26]. The analysis included 115 confirmed positive cases distributed across the study area, with the total population of each settlement as the at-risk population. Geographical coordinates from 74 households were used to locate cases within the study area. It was assumed that the number of cases in each location follows a Poisson distribution, where the expected number of cases in an area is proportional to its population size. This approach allows for the detection of statistically significant clusters by comparing observed case counts with expected values under the null hypothesis of random spatial and temporal distribution. The analysis incorporated a space-time scan statistic, which enables the identification of clusters that vary both spatially and temporally, providing insights into potential outbreak patterns and temporal trends. Additionally, the locations of the detected clusters were compared with the UBN index to assess correlations between high disease incidence and socioeconomic deprivation.

4. Results

4.1. Epidemiological Situation

This study included 2877 patients, comprising pregnant women, postpartum women, newborns, and other children. Between 2018 and 2024, the private–public healthcare implementation provided a substantial number of services, including 2575 controlled pregnancies and approximately 3900 prenatal check-ups.
Regarding infections within the EMTCT Plus framework, the evaluation of 2575 pregnant women revealed that ChD was the most prevalent condition, with 4.1% of the women testing positive. ChD cases were also detected in newborns and preexisting children born to mothers with the disease. In contrast, syphilis was only identified among pregnant women, with a prevalence of 0.8%. Notably, no cases of HIV or HBV were reported during the study period.
Among preexisting children of mothers with ChD, 205 out of 236 (86.9%) were tested, with 14 (6.8%) diagnosed as positive for T. cruzi infection. Of the affected children, 12 (85.7%) received treatment. In the case of newborns, 97 out of 111 (87.4%) were tested, and 11 (11.3%) were diagnosed with T. cruzi infection. All infected newborns (100%) received treatment.

4.2. Distribution of Chagas and Syphilis Cases

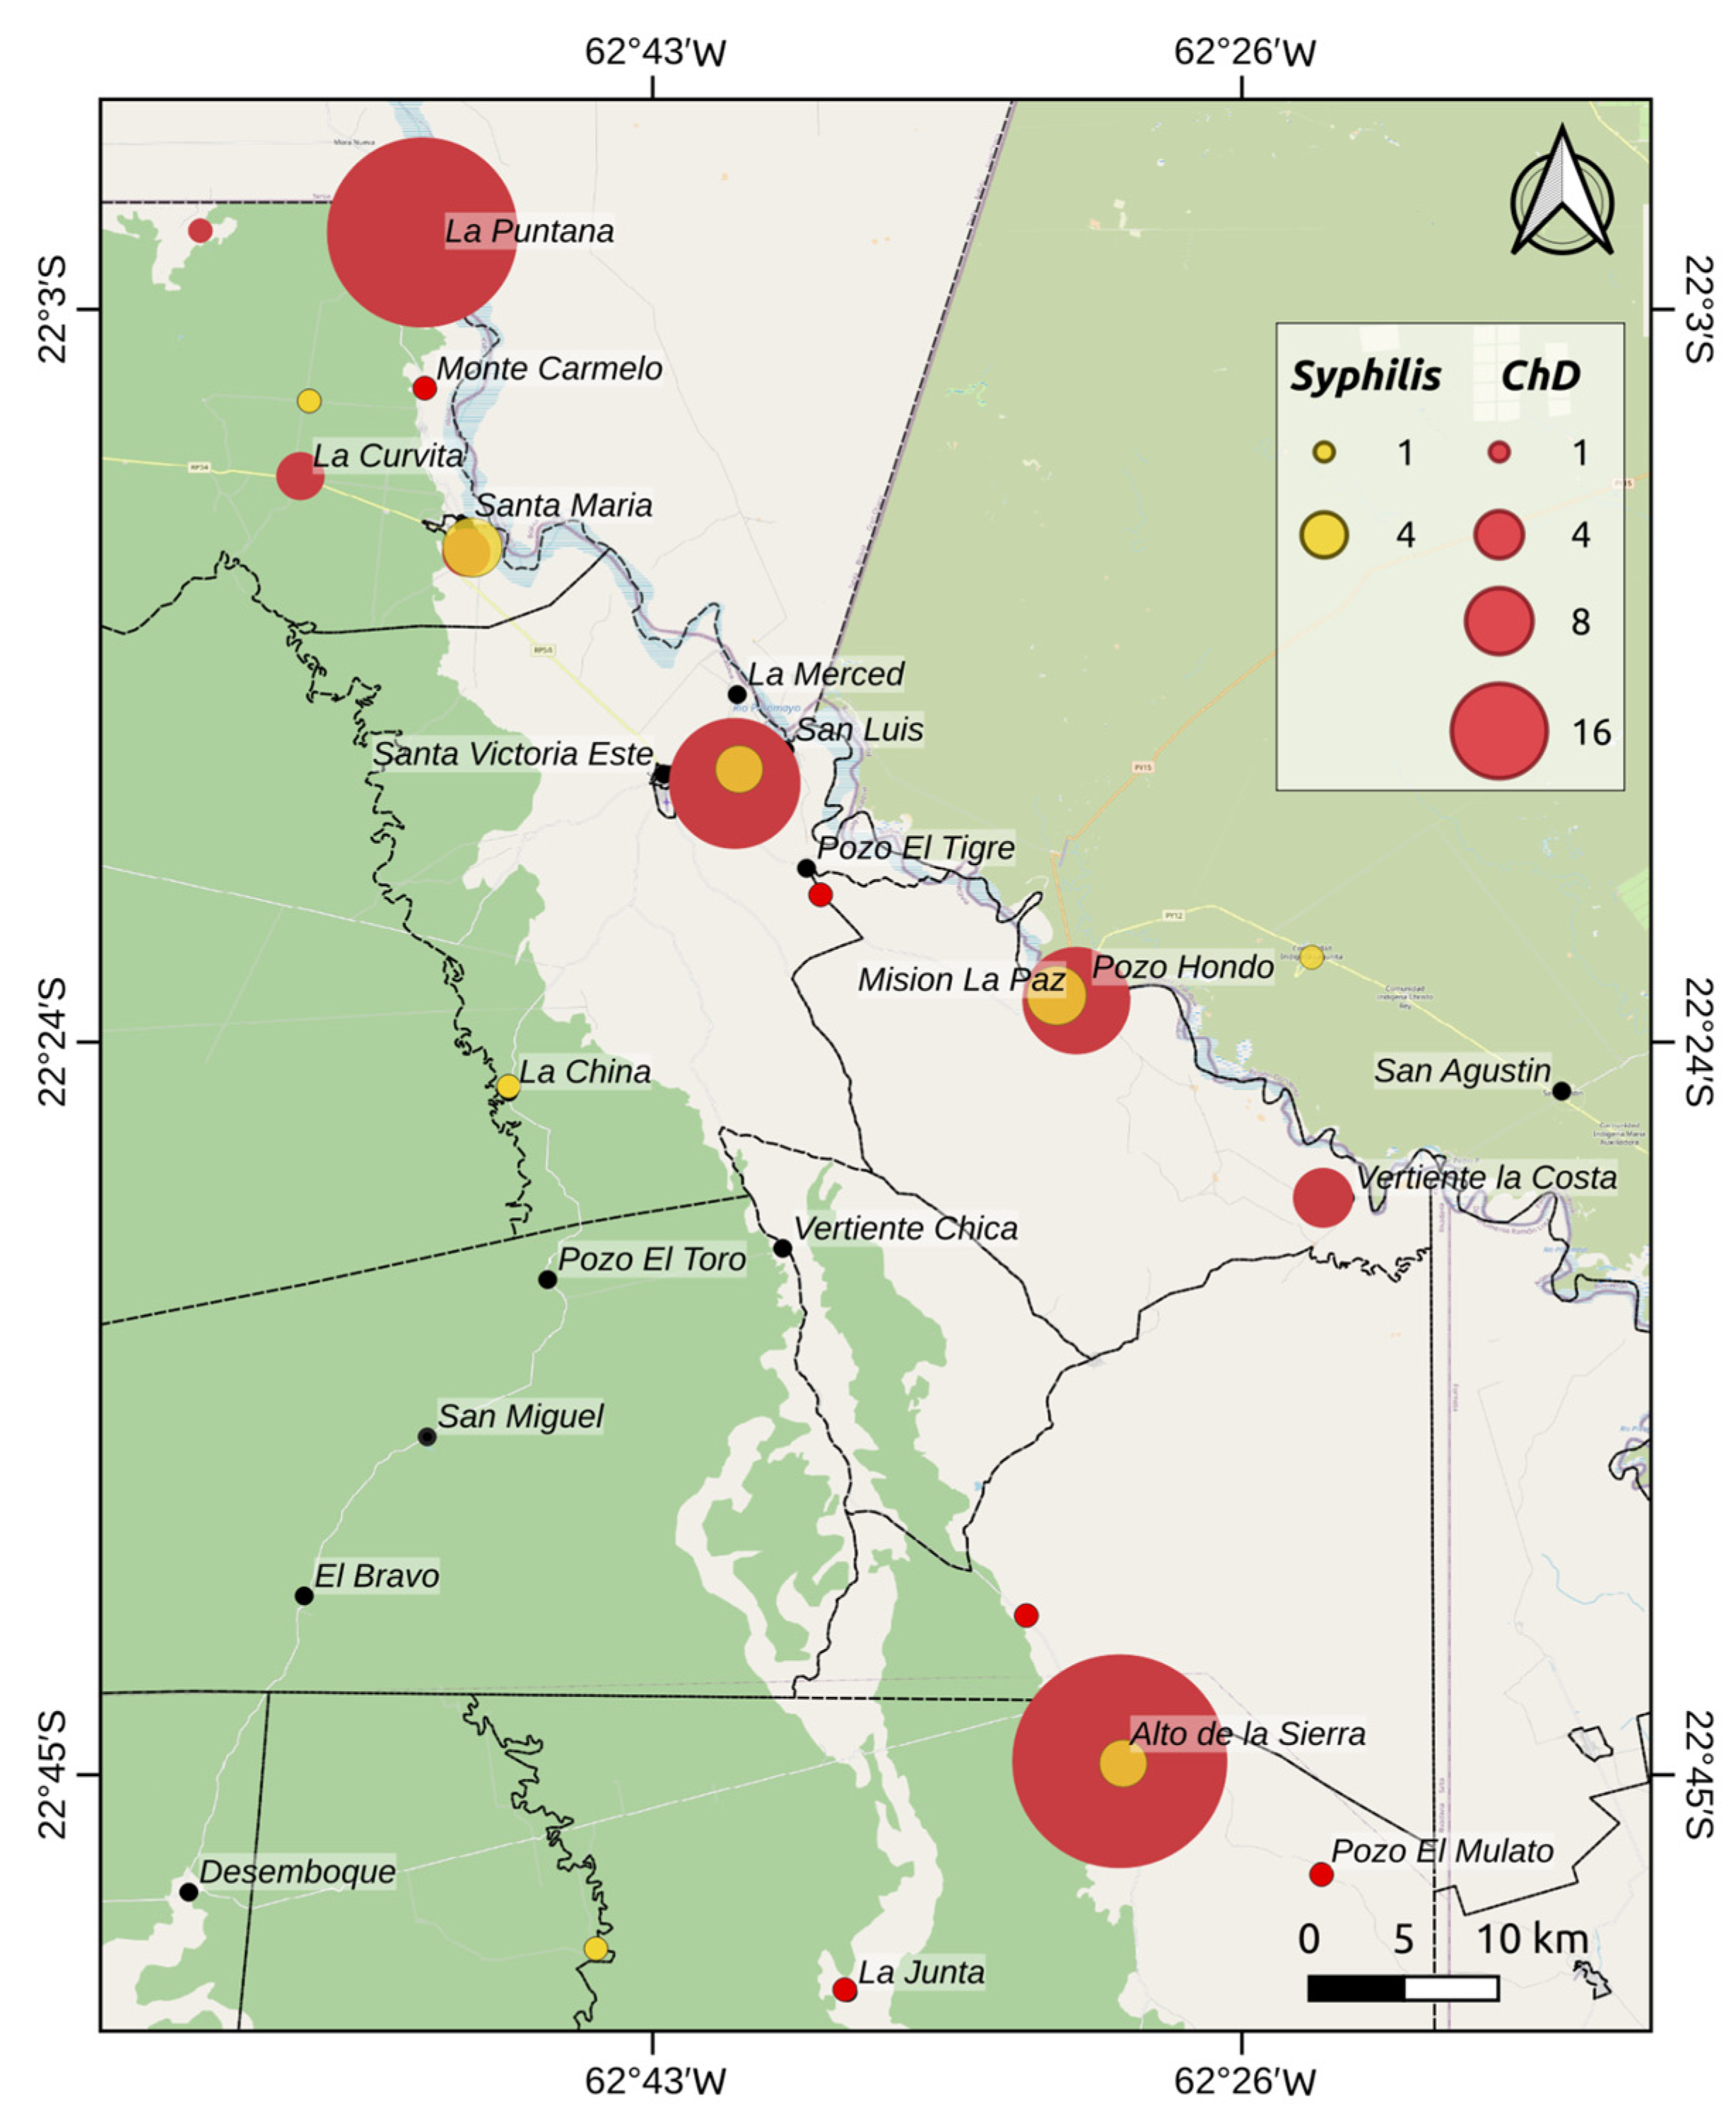
The distribution and prevalence of T. cruzi and syphilis among tested women between 2018 and 2024 varied according to settlement and country (Table 1). In Paraguay, data were available only for Pozo Hondo, where T. cruzi was detected in 10.0% of the tested women, while syphilis was found in 15.0%. In Argentina, the settlements with the highest prevalence of T. cruzi were La Junta (100.0%), San Luis (14.8%), Vertiente de la Costa (14.1%), and La Puntana (11.6%). In Alto la Sierra and Misión La Paz, infection rates were 11.3% and 6.6%, respectively. In contrast, Santa María and Pozo El Tigre exhibited the lowest rates, with 2.0% and 3.4%, respectively. Syphilis was detected in several settlements, with prevalence ranging from 1.3% (El Cañaveral) to 6.3% (Pozo La China). In Santa María and Alto la Sierra, rates of 2.5% and 2.1% were recorded, respectively. The “Others” category in Table 1 includes women tested in several smaller settlements throughout the study area whose residences were not assigned to a specific settlement at the time of data collection. Therefore, these records were grouped into a single category for descriptive purposes. Figure 2 illustrates the spatial distribution of both diseases in the study area.

4.3. Socioeconomic Analysis

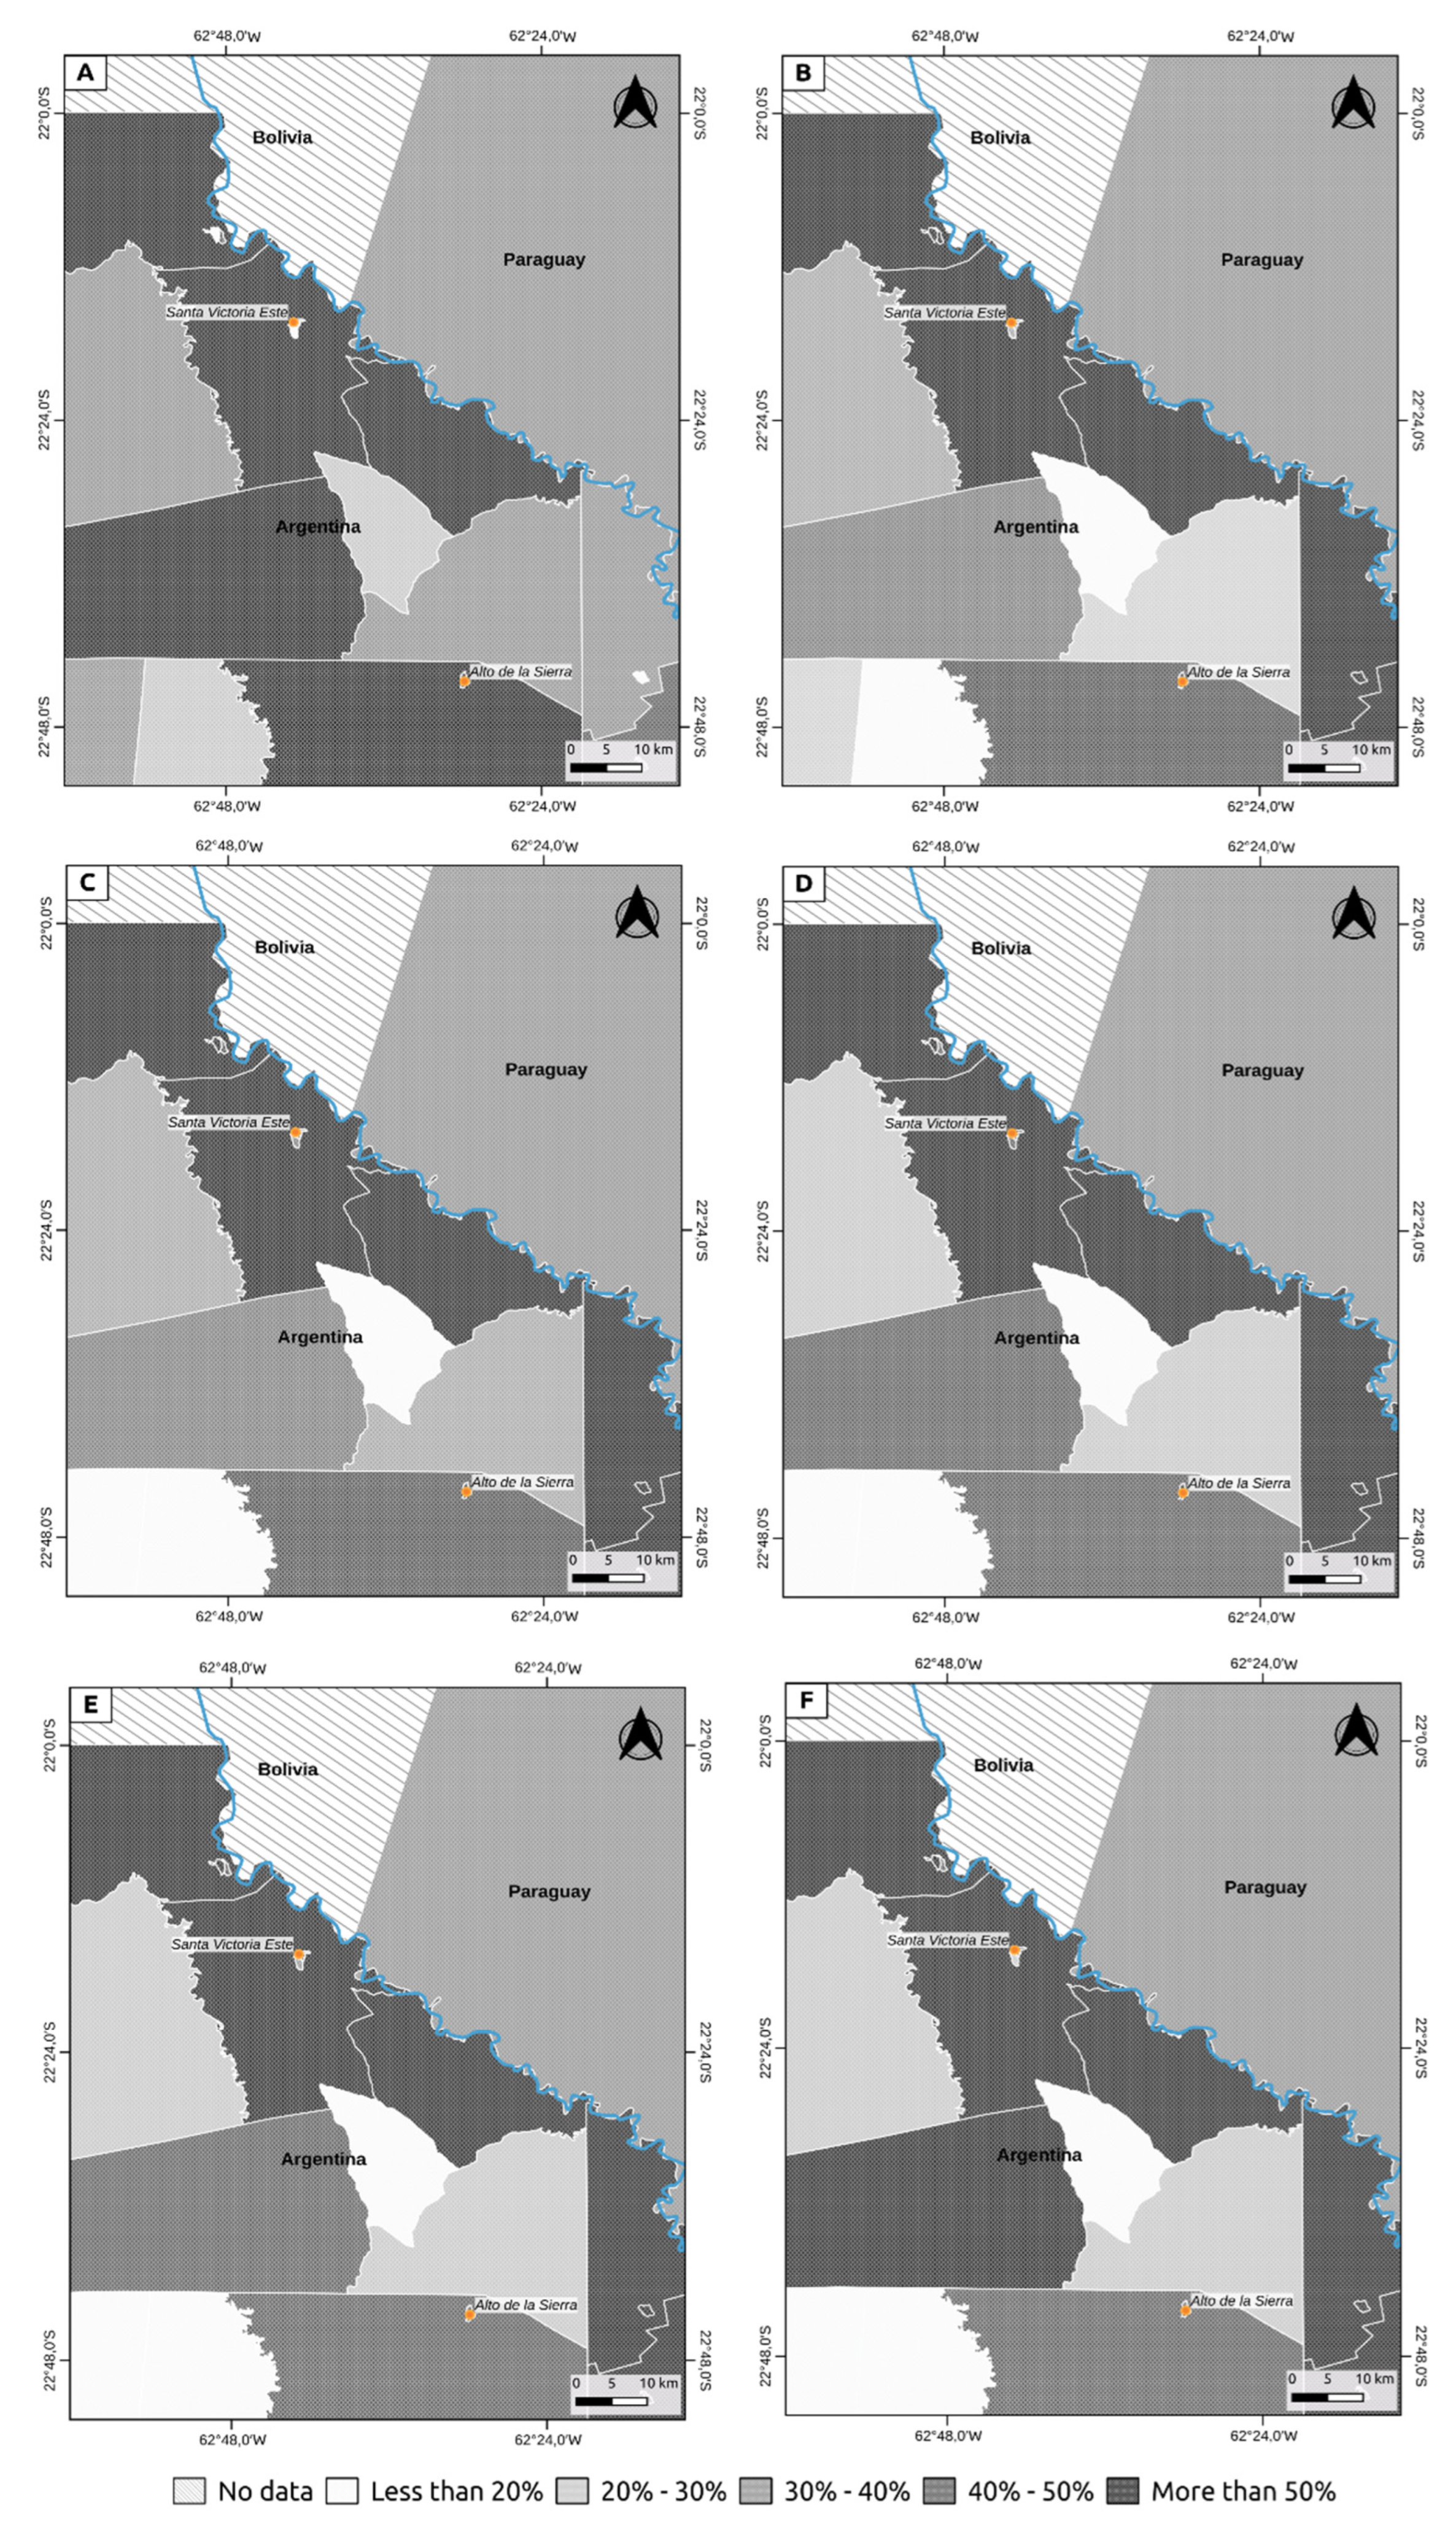
The analysis of various socioeconomic variables at the census tract level indicated that the highest levels of social vulnerability were observed in the Argentine communities of the Tri-Border region (Figure 3). The census tracts along the banks of the Pilcomayo River accounted for more than 80% of the total analysed population. In these areas, more than 50% of the population was found to have at least one unmet basic need, such as access to domestic piped water, severe overcrowding, and substandard housing conditions. The census tract of Alto la Sierra was also found to exhibit high levels of vulnerability, particularly concerning access to piped water and the availability of a flushing toilet system.

4.4. Spatio-Temporal Clustering Patterns

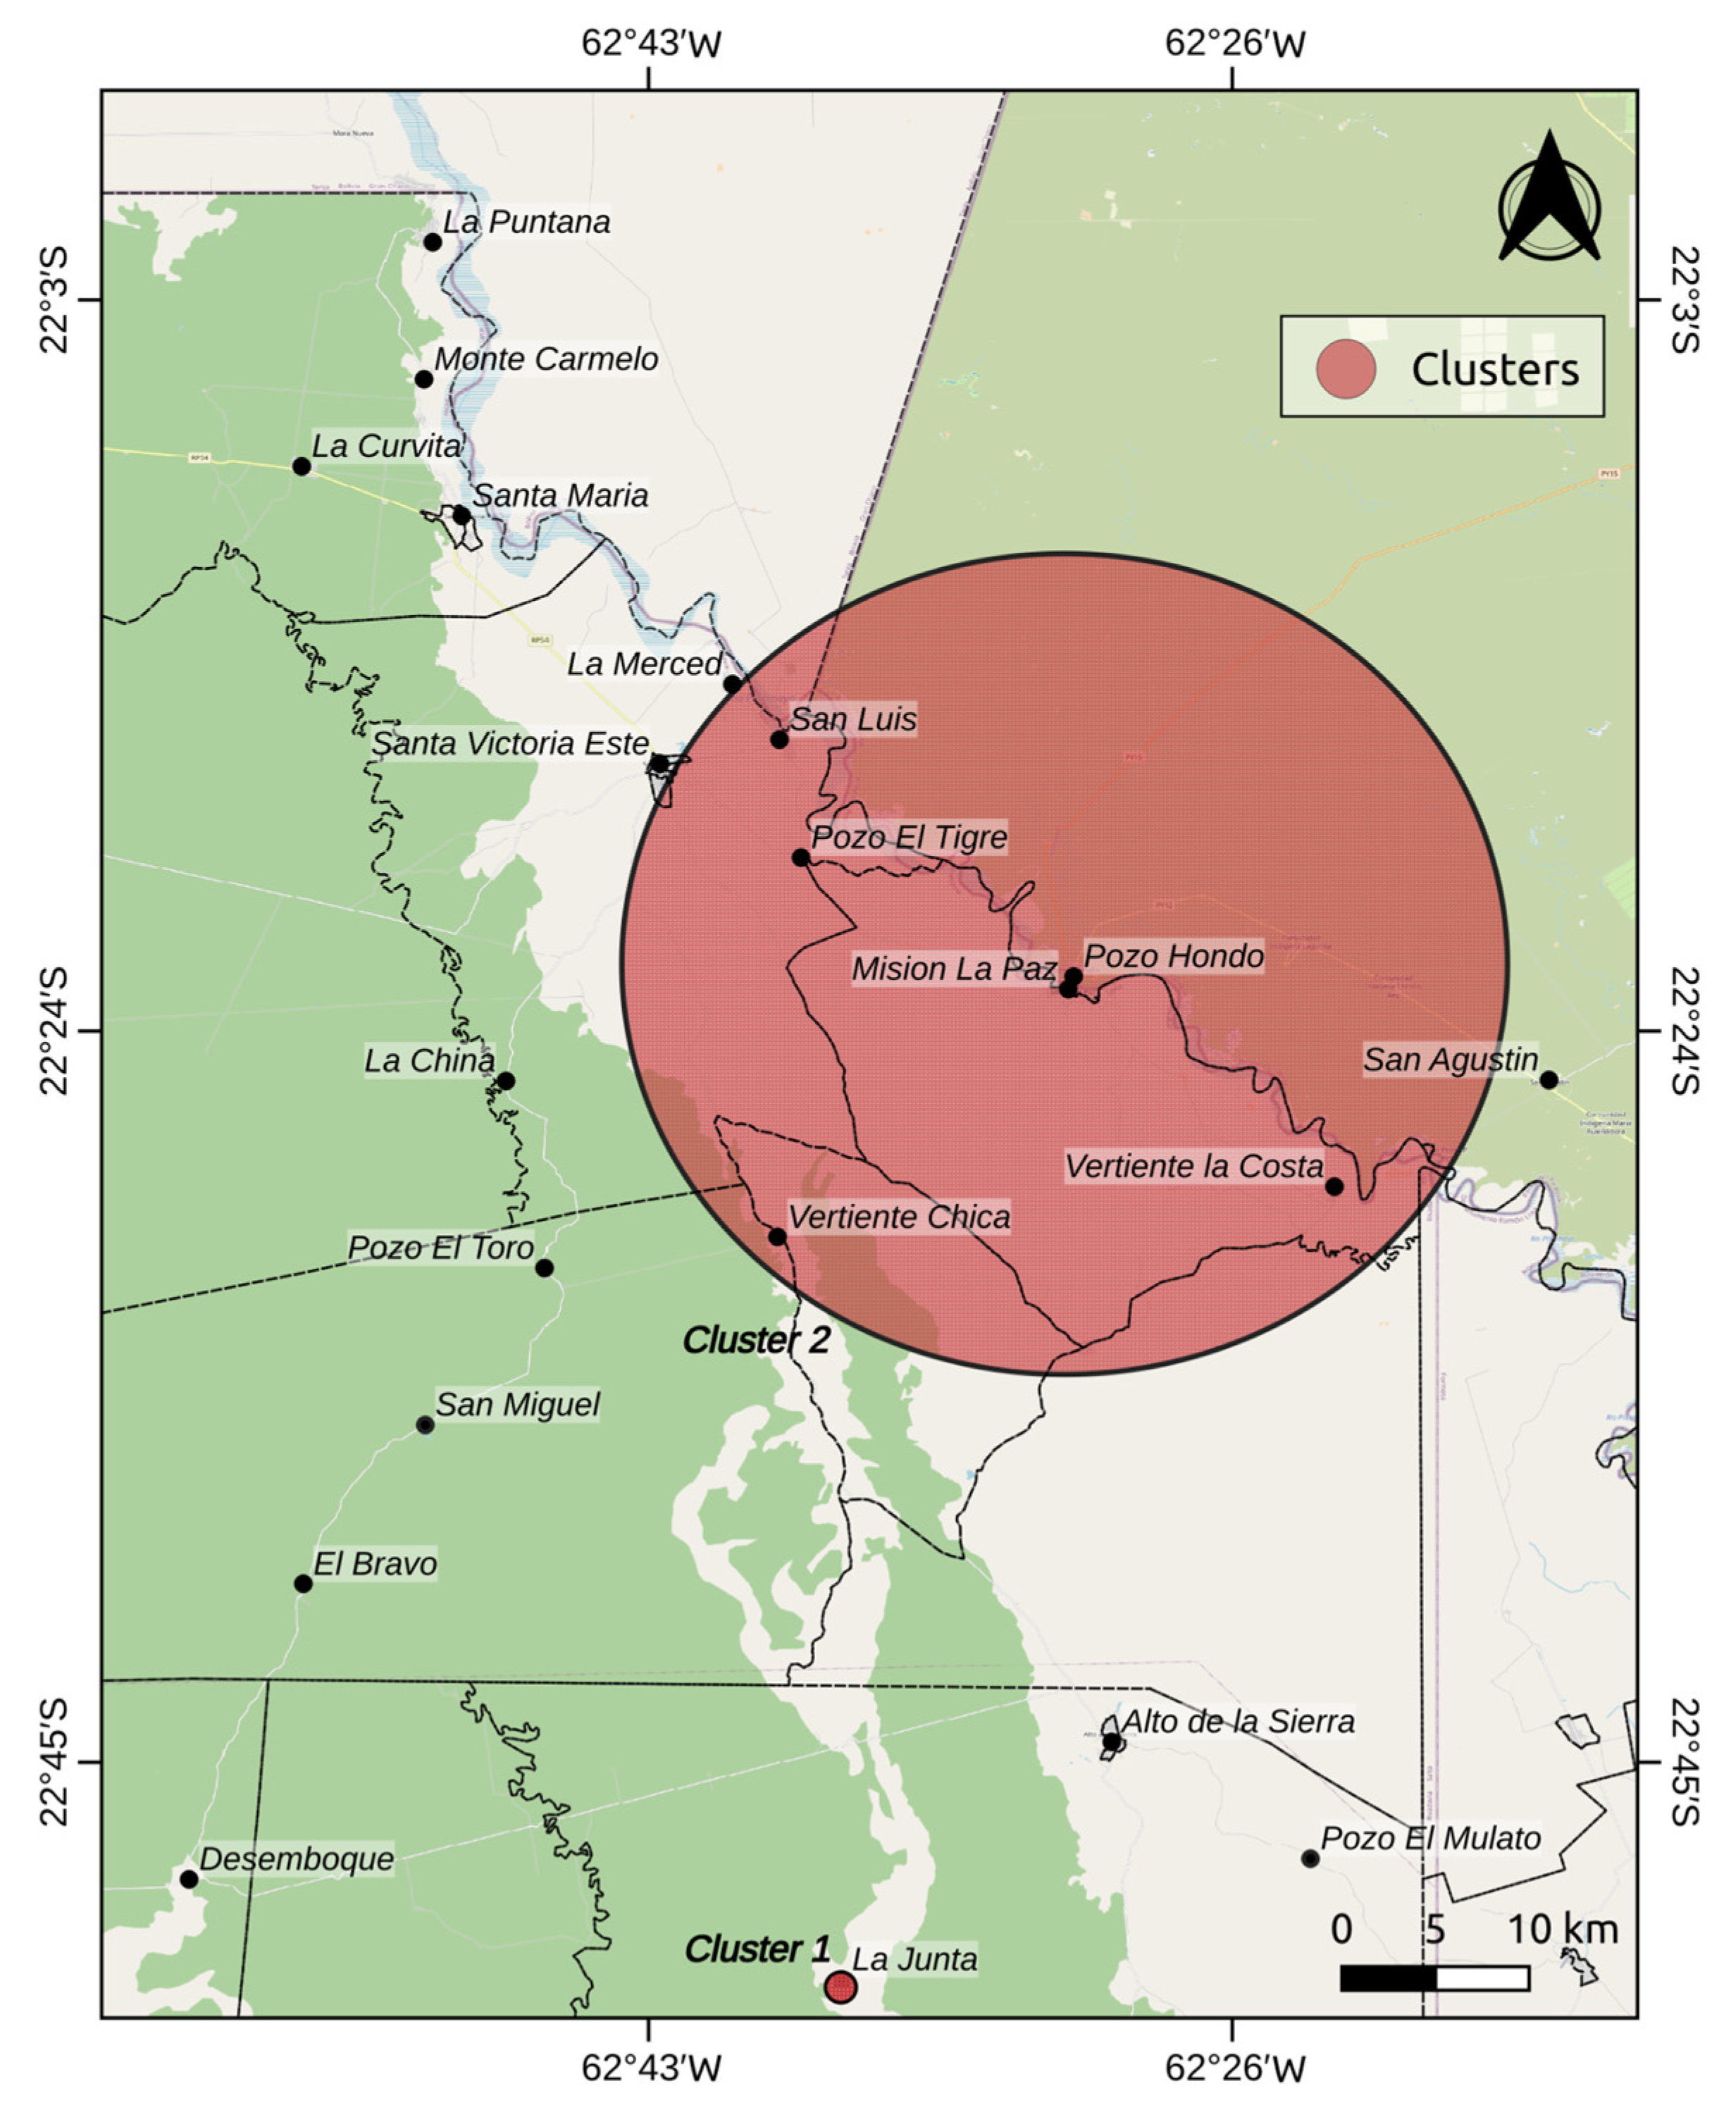
Non-random patterns were identified in the distribution of ChD cases, indicating spatio-temporal clustering. Two statistically significant, non-overlapping clusters were identified (p-value < 0.05, Table 2). Cluster 1, with a radius of 0 km, grouped four cases within a single household located in La Junta during the second half of 2018. This cluster exhibited the highest relative risk (RR = 132.43), far exceeding the expected number of cases (0.031), and showed a highly significant p-value (p < 0.001). Cluster 2, identified between 2019 and 2021, encompassed 33 cases within a radius of 21.02 km, distributed across five settlements in Argentina—Vertiente de la Costa, Misión La Paz, Vertiente Chica, Pozo el Tigre, and San Luis—as well as one settlement in Paraguay, Pozo Hondo (Figure 4). Although its relative risk was lower (RR = 2.71), it was still statistically significant (p = 0.01) and represented a substantial excess over the expected number of cases (14.89). No significant spatial clusters were found for syphilis cases.

5. Discussion

The findings of this study provide updated evidence on the distribution and dynamics of MTCT infections in a region characterised by high structural vulnerability and unequal access to healthcare services. In this context, a key finding was the identification of a substantial maternal seroprevalence of ChD (4.1%), together with the detection of two spatiotemporal clusters of cases: a household-level cluster in 2018 and a regional cluster between 2019 and 2021. These patterns suggest areas where T. cruzi infection remains concentrated and highlight the need for targeted binational strategies, particularly in areas characterised by high socioeconomic vulnerability.
A broad coverage of maternal and child healthcare services was achieved throughout the study period, as evidenced by the volume of prenatal care provided and the number of patients tested and treated. A total of 2575 pregnancies were monitored, and approximately 3900 prenatal consultations were conducted, indicating that access to essential services was successfully ensured for a substantial portion of the target population (n = 2877).
Within the framework of the EMTCT Plus initiative, screening for congenital infections among pregnant women revealed that ChD was the most prevalent condition, with a positivity rate of 4.1%. This finding is consistent with the endemic nature of T. cruzi infection in the region and highlights the ongoing risk of vertical transmission [27,28,29]. Similar studies in other endemic regions have reported comparable maternal seroprevalence rates and associated adverse neonatal outcomes, reinforcing the urgency of including T. cruzi in mandatory pregnancy screening programs [30,31]. Among children born to mothers with ChD, high testing coverage was achieved, and all confirmed congenital cases received timely treatment (100% treatment rate), illustrating the effectiveness of integrated maternal and child healthcare pathways. Nevertheless, cases confirmed only by serology after 10 months of age should be interpreted with caution, as congenital and early postnatal vector-borne transmission cannot be fully distinguished with the available data.
In contrast, syphilis was detected at a substantially lower rate (0.8%), and no cases of HIV or HBV were identified despite the approximately 95% screening coverage achieved among pregnant women. For HBV, this finding is consistent with the long-standing implementation of universal infant hepatitis B vaccination and routine antenatal screening in Argentina, which have substantially reduced the burden of HBV infection among women of reproductive age. For HIV, the absence of detected cases may reflect a genuinely low prevalence in the study population; however, the sample size limits the ability to detect rare events, and undiagnosed infections, including those occurring during the serological window period, cannot be completely excluded. Therefore, these findings should be interpreted as consistent with a low prevalence of HIV and HBV in the study population rather than as definitive evidence of their absence.
Distinct spatial patterns of ChD and syphilis prevalence were identified across settlements, requiring contextual interpretation in light of their differing epidemiological characteristics and associated sociodemographic factors [32,33,34]. As shown in Table 1, the highest prevalence of maternal ChD was recorded in census tracts located along the Pilcomayo River and near Alto la Sierra—areas characterised by higher population density. This spatial concentration of maternal ChD cases may reflect the historical endemicity of T. cruzi infection in these areas, together with persistent structural vulnerabilities and limited access to timely diagnosis and treatment [35,36]. Regarding the spatial distribution of syphilis, cases were more evenly distributed across the study area. Although the highest settlement-specific prevalence was observed in Pozo Hondo (15.0%; 3/20 women tested), this estimate should be interpreted with caution because it was based on a very small number of women and no statistically significant spatial cluster was identified in the SaTScan analysis. Consequently, this finding is more likely to reflect the small sample size than a true local hotspot, although additional surveillance in Pozo Hondo would help determine whether a higher prevalence is present. The detection of syphilis cases in multiple settlements, despite the low overall prevalence, nevertheless highlights the importance of maintaining comprehensive antenatal screening and strengthening sexual and reproductive health services throughout the region.
A descriptive comparison between the spatial distribution of positive cases and socioeconomic indicators suggested a pattern of co-occurrence with social deprivation. As illustrated in Figure 3, the census tracts located along the Pilcomayo River, where the highest prevalence of maternal T. cruzi seropositivity and syphilis was recorded, also exhibited the highest levels of unmet basic needs. Critical overcrowding (Figure 3B), lack of flushing toilet systems (Figure 3C), and poor housing conditions, including substandard roofing and flooring materials (Figure 3D,E), were consistently observed in these areas. Previous studies have associated these socioeconomic conditions with an increased risk of vector-borne and sexually transmitted infections through greater environmental exposure and reduced access to hygiene and healthcare services [35,37,38,39]. Likewise, Alto la Sierra presented multiple housing-related vulnerabilities. Although the spatial overlap between positive cases and structural deprivation, summarized by the Unmet Basic Needs Index (Figure 3F), is consistent with the broader literature on the social determinants of health, these findings should be interpreted as descriptive observations rather than evidence of a statistical association. Further studies incorporating formal statistical analyses and entomological data are needed to better understand the relationship between socioeconomic vulnerability and the spatial distribution of these infections.
The spatiotemporal analysis provided additional insight into the spatial and temporal distribution of maternal T. cruzi seropositivity by identifying two statistically significant clusters, each with distinct characteristics in terms of magnitude, geographic extent, and temporal distribution (Table 2, Figure 4). Cluster 1, concentrated within a single household in La Junta, exhibited an exceptionally high relative risk and may reflect a localized aggregation of cases in a setting of extreme social and environmental vulnerability. Although the detection of multiple cases within one household is compatible with possible intradomiciliary transmission, the absence of entomological data precludes confirmation of the underlying transmission mechanism. Cluster 2, spanning multiple settlements across Argentina and Paraguay, represented a broader cross-border spatial pattern. Although its relative risk was lower than that of Cluster 1, the number of observed cases substantially exceeded the expected number, indicating a persistent spatial concentration of maternal T. cruzi seropositivity during 2019–2021.
Previous studies have shown that the spatial distribution of T. cruzi infection is influenced by ecological factors. In northern Argentina and Chile, fine-scale analyses demonstrated that infestation and infection patterns were more closely associated with land cover and host dynamics than with administrative boundaries, highlighting the importance of geographically targeted interventions in environmentally and socially vulnerable border regions [40,41]. By contrast, no statistically significant clusters of syphilis cases were identified. This finding may reflect both the distinct epidemiology of syphilis, which is strongly influenced by human mobility and sexual networks [34,37], and the limited number and geographic dispersion of cases detected in the present study (n = 23), which reduced the statistical power to detect localized clusters [42,43]. Therefore, the absence of significant clusters should not be interpreted as evidence that localized clusters of syphilis cases do not exist, but rather that the available data were insufficient to identify them. Longer surveillance periods and larger datasets will be needed to better characterize the spatial distribution of syphilis in this region.
Despite these contributions, important challenges remain for research and surveillance in this region. The absence of data from the Bolivian side of the tri-border area reflects the broader difficulties of data sharing and surveillance integration across international borders, limiting the ability to fully characterize transmission dynamics in this highly connected epidemiological setting. In addition, although the screening strategy achieved approximately 95% coverage of pregnant women in the participating communities, the NGO-led recruitment approach may have introduced some degree of selection bias, as women who were not reached or who did not participate may have differed from those included in the study. Nevertheless, the high screening coverage likely reduced the magnitude of this potential bias. Strengthening cross-border surveillance systems and harmonizing data collection between neighboring countries will be essential to improve the identification of priority areas for intervention and to support coordinated prevention, follow-up, and treatment strategies.
Building on the findings of the present study, future research should aim to directly estimate congenital transmission rates and identify the maternal, parasitological, environmental, and socioeconomic factors associated with transmission. Incorporating systematic molecular diagnosis in newborns, extending follow-up periods, and applying formal spatial and statistical analyses would complement the descriptive and spatiotemporal approaches presented here, providing a more comprehensive understanding of the determinants and geographic distribution of MTCT infections in this vulnerable border region.

6. Conclusions

The findings of this study highlight the effectiveness of an integrated maternal and child healthcare strategy in a context of high social vulnerability, as demonstrated by the broad screening coverage, follow-up, and timely treatment achieved within the EMTCT Plus initiative. The identification of distinct spatial patterns of maternal T. cruzi seropositivity and their co-occurrence with areas of greater structural deprivation underscores the importance of sustaining targeted interventions that address both healthcare access and the broader social determinants of health. In addition, the detection of spatiotemporal clusters identified areas where T. cruzi infection remained concentrated over time, supporting the need for coordinated binational surveillance and control strategies in border regions facing shared epidemiological challenges. Strengthening surveillance systems, ensuring equitable access to early diagnosis and treatment, and promoting cross-border collaboration will be essential to advance the elimination of mother-to-child transmission of these infections. Overall, this study provides valuable evidence to support the development of more equitable, context-sensitive public health policies aimed at reducing health disparities in historically underserved populations.

Author Contributions

C.R.G., S.Á., M.F., F.C., V.A. and M.V.P. contributed to the conception and design of the work; C.R.G., S.Á. and K.C. contributed to acquisition, analysis and interpretation of data. C.R.G. drafted the work, while V.A. and M.V.P. revised it. All authors approve the submitted version and agree to be personally accountable for their contributions and ensure that questions related to the accuracy or integrity of any part of the work, even ones in which the author was not personally involved, are appropriately investigated, resolved, and the resolution documented in the literature. All authors have read and agreed to the published version of the manuscript.

Funding

This study was funded as a private–public collaboration between Fundación Mundo Sano, Asociación Regional para el Desarrollo Sanitario (ADESAR), the Ministerio de Salud Pública (Salta, Argentina), and the Municipality of Santa Victoria Este (Salta, Argentina).

Institutional Review Board Statement

This study was approved by the Research Ethics Committee of the Centro de Educación Médica e Investigaciones Clínicas “Norberto Quirno” (CEMIC), Buenos Aires (Argentina) (Ref. No.: 1232), and the Ethical Committee of the Ministerio de Salud Púbica y Bienestar Social of Paraguay (Ref. No. SIMESE N° 76.3521202, dated 15 June 2018).

Informed Consent Statement

Individual informed consent was deemed unnecessary according to national regulations, Guide for Investigations of Human Health published by Argentina’s Ministry of Health (items A3b and B1.1.5b) [44]. Our study adhered to the Declaration of Helsinki.

Data Availability Statement

The datasets used and/or analysed during the current study are available from the corresponding author on reasonable request.

Acknowledgments

We would like to thank all members of Fundación Mundo Sano, especially the administrative staff and field team, as well as collaborating public and private institutions who have provided feedback or contributed to the implementation, namely Dirección de Epidemiología of Ministerio de Salud Pública (Salta, Argentina) and XVI Región Sanitaria Boquerón, Ministerio de Salud Pública y Bienestar Social (Mariscal José Félix Estigarribia, Paraguay). Finally, we acknowledge the primary health team (sanitary agents, nurses and other professionals) from the operative areas of Santa Victoria Este and Alto la Sierra in Argentina and the UAFs from San Agustín and Pozo Hondo (Paraguay), as well as the expert drivers from the Ministerio de Salud Pública (Salta, Argentina). All authors have read and agreed to the published version of the manuscript.

Conflicts of Interest

The authors declare no competing interests.

References

  1. WHO. Governance for the Validation of Elimination of Mother-to-Child Transmission of HIV, Syphilis and Hepatitis B Virus: An Overview of Validation Structures and Responsibilities at National, Regional and Global Levels; World Health Organization: Geneva, Switzerland, 2022. [Google Scholar]
  2. WHO. Global Health Sector Strategies on HIV, Viral Hepatitis and Sexually Transmitted Infections for the Period 2022–2030; World Health Organization: Geneva, Switzerland, 2022. [Google Scholar]
  3. Organización Panamericana de la Salud. Nuevo Marco para Eliminar la Transmisión Materno Infantil de Cuatro Enfermedades; OPS: Washington, DC, USA, 2017; Available online: https://www.paho.org/hq/index.php?option=com_content&view=article&id=13567 (accessed on 5 January 2026).
  4. Freilij, H. ETMI-PLUS, iniciativa que deberíamos implementar. Rev. Hosp. Niños 2018, 60, 141–143. Available online: http://revistapediatria.com.ar/wp-content/uploads/2018/07/269-01-ETMI-Plus-inicia-va-que-deberi%CC%81amos-implementar.pdf.
  5. Pan American Health Organization; World Health Organization. EMTCT Plus: Framework for Elimination of Mother-to-Child Transmission of HIV, Syphilis, Hepatitis B and Chagas; PAHO: Washington, DC, USA, 2017. [Google Scholar]
  6. Taylor, M.M.; Wi, T.; Gerbase, A.; Thwin, S.S.; Gottlieb, S.; Babovic, M.T.; Low-Beer, D.; Alonso, M.; Mello, M.B.; Ishikawa, N.; et al. Assessment of country implementation of the WHO global health sector strategy on sexually transmitted infections (2016–2021). PLoS ONE 2022, 17, e0263550. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Miranda, A.E.; Santos, P.C.; Coelho, R.A.; Pascom, A.R.P.; de Lannoy, L.H.; Ferreira, A.C.G.; Gaspar, P.C.; Maciel, E.L.; Barreira, D.; Pereira, G.F.M. Perspectives and challenges for mother-to-child transmission of HIV, hepatitis B, and syphilis in Brazil. Front. Public Health 2023, 11, 1182386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Cohn, J.; Owiredu, M.N.; Taylor, M.M.; Easterbrook, P.; Lesi, O.; Francoise, B.; Broyles, L.N.; Mushavi, A.; Van Holten, J.; Ngugi, C.; et al. Eliminating mother-to-child transmission of human immunodeficiency virus, syphilis and hepatitis B in sub-Saharan Africa. Bull. World Health Organ. 2021, 99, 287. [Google Scholar] [PubMed]
  9. Organización Panamericana de la Salud. Plan de Acción para la Prevención y el Control de la Infección por el VIH y las Infecciones de Transmisión Sexual 2016–2021. Available online: https://iris.paho.org/bitstream/handle/10665.2/34079/DC552017-spa.pdf (accessed on 16 November 2025).
  10. Ministerio de Salud de la Nación Argentina. Algoritmos de Diagnóstico y Tratamiento para el Control de las Infecciones Perinatales por VIH, Sífilis, Hepatitis B y Chagas: Iniciativa ETMI-PLUS; Ministerio de Salud: Buenos Aires, Argentina, 2024; Available online: https://www.argentina.gob.ar/sites/default/files/2024/04/algoritmos_d_diag_y_trat_ip_vih_sifilis_vhb_y_chagas_2662024_0.pdf (accessed on 16 November 2025).
  11. Domingues, R.M.; Leal, M.C. Incidence of congenital syphilis and factors associated with vertical transmission: Data from the Birth in Brazil study. Cad. Saude Publica 2016, 32, e00082415. [Google Scholar] [CrossRef] [Scilit]
  12. Nonato, S.M.; Melo, A.P.S.; Guimarães, M.D.C. Syphilis in pregnancy and factors associated with congenital syphilis in Belo Horizonte-MG, Brazil, 2010–2013. Epidemiol. Serv. Saude 2015, 24, 681–694. [Google Scholar] [CrossRef] [Scilit]
  13. Kamanzi, J.; Richter, S.M.; Paul, P.; Jarvis, K. Social determinants of health that influence the uptake of the PMTCT program. Int. J. Nurs. Health Care Res. 2022, 5, 1362. [Google Scholar] [CrossRef] [Scilit]
  14. Anyaegbunam, E.N.; Ogbonnaya, C.E. Roles of social determinants of health in elimination of mother-to-child transmission of HIV/AIDS in Nigeria. Journal of Psychology and Allied Disciplines 2022, 1. Available online: https://jpadfunai.com/index.php/JPAD/article/view/8.
  15. Elias, D.E.; Cardinal, M.V.; Macchiaverna, N.P.; Enriquez, G.F.; Gürtler, R.E.; Gaspe, M.S. Domestic (re)infestation risk with the main vector Triatoma infestans increases with surrounding green vegetation and social vulnerability in the Argentine Chaco. Parasites Vectors 2024, 17, 240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Maldonado, P.; Hohne, E.; Naumann, M. Atlas del Gran Chaco Americano; Ministerio de Educación: Buenos Aires, Argentina, 2006. [Google Scholar]
  17. Pan American Health Organization. Proyecto Hacia la Salud Universal de la Población del Gran Chaco Suramericano 2016–2019: Resultados del Componente Salud Materno Infantil; PAHO: Washington, DC, USA, 2020. [Google Scholar]
  18. Hotez, P.J.; Kamath, A. Neglected tropical diseases in sub-Saharan Africa: Review of their prevalence, distribution, and disease burden. PLoS Negl. Trop. Dis. 2009, 3, e412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Signor, M.; de Lima Spagnolo, L.M.; Oliveira Tomberg, J.; Gobatto, M.; Sevilha Stofel, N. Spatial distribution and characterization of cases of congenital syphilis. Rev. Enferm. UFPE 2018, 12, 398–406. [Google Scholar] [CrossRef] [Scilit]
  20. Instituto Nacional de Estadística y Censos (INDEC). Sistema Redatam. Available online: https://redatam.indec.gob.ar/ (accessed on 20 July 2025).
  21. Defensoría de los Derechos de las Niñas, Niños y Adolescentes. Informe de Situación: Niñas, Niños y Adolescentes de Comunidades Indígenas del Chaco Salteño; Defensoría de los Derechos de las Niñas, Niños y Adolescentes: Buenos Aires, Argentina, 2020. [Google Scholar]
  22. Crudo, F.; Piorno, P.; Krupitzki, H.; Guilera, A.; López-Albizu, C.; Danesi, E.; Scollo, K.; Lloveras, S.; Mir, S.; Álvarez, M.; et al. How to implement the framework for the elimination of mother-to-child transmission of HIV, syphilis, hepatitis B and Chagas (EMTCT Plus) in a disperse rural population from the Gran Chaco region. PLoS Negl. Trop. Dis. 2020, 14, e0008078. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Falleti, T.G.; Cunial, S.L.; Sotelo, S.B.; Crudo, F.; Davis, L. State and NGO coproduction of health care in the Gran Chaco. World Dev. 2024, 176, 106502. [Google Scholar] [CrossRef] [Scilit]
  24. Ministerio de Salud de la Nación. Algoritmos de Diagnóstico y Tratamiento para el Control de las Infecciones Perinatales por VIH, Sífilis, Hepatitis B y Chagas. Iniciativa ETMI-PLUS. Edición 2025; Ministerio de Salud de la Nación: Buenos Aires, Argentina, 2025; Available online: https://www.argentina.gob.ar/sites/default/files/algoritmos_vih_sifilis_hepatitis_b_y_chagas_2025_1352025.pdf?utm_source=chatgpt.com (accessed on 15 January 2026).
  25. Dirección General de Estadística; Encuestas y Censos. Censo Nacional de Población y Viviendas 2022. Paraguay. Available online: https://www.ine.gov.py/censo2022/ (accessed on 5 November 2025).
  26. Kulldorff, M. SaTScan™ Software for Spatial and Space-Time Scan Statistics (Version 10.2.5). 2021. Available online: https://www.satscan.org/ (accessed on 10 November 2025).
  27. Colussi, C.; Stafuza, M.; Nepote, M.; Mendicino, D. Seroprevalence of Chagas disease in urban and rural indigenous populations of the south of Gran Chaco. Rev. Soc. Bras. Med. Trop. 2022, 55, e0479-2021. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Colussi, C.; Nepote, M.; Chiaraviglio, R.; Mendicino, D. Chagas disease: Seroprevalence and associated factors in indigenous communities of the southern limit of Argentine Chaco. Trop. Med. Infect. Dis. 2023, 8, 64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Weinberg, D.; Casale, M.F.; Cejas, R.G.; Hoyos, R.; Periago, M.V.; Segura, E.; Abril, M.C. Chagas prevention and control in an endemic area from the Argentinian Gran Chaco region: Data from 14 years of uninterrupted intervention. PLoS Negl. Trop. Dis. 2023, 17, e0011410. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Lynn, M.K.; Rodriguez Aquino, M.S.; Cornejo Rivas, P.M.; Kanyangarara, M.; Self, S.C.; Campbell, B.A.; Nolan, M.S. Chagas disease maternal seroprevalence and maternal–fetal health outcomes in a parturition cohort in western El Salvador. Trop. Med. Infect. Dis. 2023, 8, 233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. López-Monteon, A.; Montero, H.; González-Constantino, R.S.; Limón-Flores, A.Y.; Varela-Cardoso, M.; Luna-Hernández, G.; Dumonteil, E.; Ramos-Ligonio, A. Seroprevalence of Trypanosoma cruzi infection in pregnant women suggests a high risk for congenital transmission in Central Veracruz, Mexico. Acta Parasitol. 2020, 65, 661–668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Cucunubá, Z.M.; Gutiérrez-Romero, S.A.; Ramírez, J.D.; Velásquez-Ortiz, N.; Ceccarelli, S.; Parra-Henao, G.; Henao-Martínez, A.F.; Rabinovich, J.; Basáñez, M.-G.; Nouvellet, P.; et al. The epidemiology of Chagas disease in the Americas. Lancet Reg. Health Am. 2024, 37, 100881. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Boukaabar, M.; Oduro, B.; Chataa, P. Congenital transmission of Chagas disease: The role of newborn therapy on the disease’s dynamics. PLoS ONE 2024, 19, e0308136. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Garnett, G.P.; Aral, S.O.; Hoyle, D.V.; Cates, W., Jr.; Anderson, R.M. The natural history of syphilis: Implications for the transmission dynamics and control of infection. Sex. Transm. Dis. 1997, 24, 185–200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Fernández, M.D.P.; Gaspe, M.S.; Gürtler, R.E. Inequalities in the social determinants of health and Chagas disease transmission risk in indigenous and creole households in the Argentine Chaco. Parasites Vectors 2019, 12, 184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Llovet, I.; Dinardi, G.; De Maio, F.G. Mitigating social and health inequities: Community participation and Chagas disease in rural Argentina. In Latin American Perspectives on the Sociology of Health and Illness; Routledge: New York, NY, USA, 2020; pp. 89–102. [Google Scholar]
  37. DiOrio, D.; Kroeger, K.; Ross, A. Social vulnerability in congenital syphilis case mothers: Qualitative assessment of cases in Indiana, 2014 to 2016. Sex. Transm. Dis. 2018, 45, 447–451. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Busza, J.; Walker, D.; Hairston, A.; Gable, A.; Pitter, C.; Lee, S.; Katirayi, L.; Simiyu, R.; Mpofu, D. Community-based approaches for prevention of mother to child transmission in resource-poor settings: A social ecological review. J. Int. AIDS Soc. 2012, 15, 17373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Gürtler, R.E.; del Pilar Fernández, M.; Cardinal, M.V. Eco-epidemiology of vector-borne transmission of Trypanosoma cruzi in domestic habitats. In Triatominae: The Biology of Chagas Disease Vectors; Springer: Cham, Switzerland, 2021; pp. 447–489. [Google Scholar]
  40. Weinberg, D.; Porcasi, X.; Lanfri, S.; Abril, M.; Scavuzzo, C.M. Spatial analyses of triatomine infestation indices and their association to control actions and environmental variables during a 5-year intervention period. Acta Trop. 2018, 188, 41–49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Ihle-Soto, C.; Costoya, E.; Correa, J.P.; Bacigalupo, A.; Cornejo-Villar, B.; Estadella, V.; Solari, A.; Ortiz, S.; Hernández, H.J.; Botto-Mahan, C.; et al. Spatio-temporal characterization of Trypanosoma cruzi infection in non-domestic foci of Chile. PLoS Negl. Trop. Dis. 2019, 13, e0007170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Wartenberg, D.; Greenberg, M. Detecting disease clusters: The importance of statistical power. Am. J. Epidemiol. 1990, 132, 156–166. [Google Scholar] [CrossRef] [Scilit]
  43. Dalmaijer, E.S.; Nord, C.L.; Astle, D.E. Statistical power for cluster analysis. BMC Bioinform. 2022, 23, 205. [Google Scholar] [CrossRef] [Scilit]
  44. Guía para Investigaciones en Salud Humana. Ministerio de Salud (AR); 2011. Available online: http://www.msal.gov.ar/dis/wp-content/uploads/sites/11/2016/06/Guia_en_baja.pdf (accessed on 5 July 2026).
Figure 1. Study area within the Gran Chaco Region in the tri-border between Argentina, Bolivia, and Paraguay (right quadrant). Map detailing the settlements in the border regions between the three countries (left quadrant). Maps created with QGIS 3.4 open-source software.
Tropicalmed 11 00188 g001
Figure 2. Distribution of Chagas Disease (in red) and Syphilis (in yellow) cases by settlement in the border area between Argentina and Paraguay, Gran Chaco Region. The diameter of each circle represents the number of households with positive cases aggregated by settlement.
Tropicalmed 11 00188 g002
Figure 3. Socioeconomic situation in the Gran Chaco Region between Argentina and Paraguay. (A) Households without access to piped water for drinking and cooking; (B) Households experiencing critical overcrowding (more than three persons per room); (C) Households without a flushing toilet system (button, chain, or tank); (D) Households without a type 1 roof covering (membrane, tile, slab, or shingle); (E) Households without a type 1 floor covering (ceramic, tile, mosaic, marble, wood, or carpet); (F) Households classified as having Unmet Basic Needs (UBN).
Tropicalmed 11 00188 g003
Figure 4. Statistically significant spatio-temporal clusters of ChD cases in the Gran Chaco Region between Argentina and Paraguay.
Tropicalmed 11 00188 g004
Table 1. Prevalence of T. cruzi and Syphilis cases among tested women by settlement in Paraguay and Argentina (2018–2024). Values are presented as n (%); 95% confidence intervals (Wilson score) are shown in parentheses.
CountrySettlementTotal Tested WomenNumber of T. cruzi Positive (%) [95% CI]Number of Syphilis Positive (%) [95% CI]
ParaguayPozo Hondo202 (10.0, 2.8–30.1)3 (15.0, 5.2–36.0)
San Agustin71--
ArgentinaLa Merced44-2 (4.5, 1.3–15.2)
Misión la Paz22615 (6.6, 4.1–10.5)4 (1.8, 0.7–4.5)
Vertiente de la Costa7110 (14.1, 7.8–24.1)-
Pozo La China16-1 (6.3, 1.1–28.3)
San Luis548 (14.8, 7.7–26.6)-
Santa María2034 (2.0, 0.8–4.9)5 (2.5, 1.1–5.6)
Pozo El Tigre592 (3.4, 0.9–11.5)1 (1.7, 0.3–9.0)
Pozo El Toro21--
La Puntana24128 (11.6, 8.1–16.2)-
Monte Carmelo311 (3.2, 0.6–16.2)1 (3.2, 0.6–16.2)
La Curvita764 (5.3, 2.1–12.8)-
Santa Victoria Este/El Cañaveral799 (11.4, 6.1–20.4)1 (1.3, 0.2–6.8)
Vertiente Chica1--
Alto la Sierra23927 (11.3, 7.8–16.1)5 (2.1, 0.9–4.8)
Desemboque5--
El Bravo9--
La Junta44 (100, 51.0–100.0)-
Pozo el Mulato161 (6.3, 1.1–28.3)-
Others *1087--
* Others: Includes women tested in smaller settlements whose residences were not assigned to a specific settlement at the time of data collection. This category comprises Sauzalito, San Bernardo, Bajo Grande, Pozo El Mulato, La Esperanza, Pozo El Bravo, Las Mojarras, La Carneada, Morón, and Pozo Los Ranchos.
Table 2. Clusters detected for the distribution of Chagas disease cases using the discrete Poisson model.
Clusters Detected C luster 1Cluster 2
Overlap with clustersNo OverlapNo Overlap
Coordinates/radius(22.85 S, 62.62 W)/0 km(22.36 S, 62.52 W)/21.02 km
Time frame1 June 2018 to 31 December 20181 January 2019 to 31 December 2021
Number of cases433
Expected cases0.03114.89
Annual cases/100,000114,631.91986.6
Observed/expected127.862.22
Relative risk132.432.71
Log likelihood ratio15.509.89
p-value0.000062 ***0.01 *
Note: * p ≤ 0.01; *** p ≤ 0.001.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.