Article

Occupational Health and Safety Practices in Relation to Occupational Injuries Among Iron and Steel Workers


by
Saumu Shabani
1,
Bente Elisabeth Moen
2,*,
Wakgari Deressa
3 and
Simon Henry Mamuya
1
1
Department of Environmental and Occupational Health, School of Public Health and Social Sciences, Muhimbili University of Health and Allied Sciences, Dar es Salaam 11103, Tanzania
2
Department of Global Public Health and Primary Care, Centre for International Health, University of Bergen, 5020 Bergen, Norway
3
Department of Epidemiology and Biostatistics, School of Public Health, College of Health Sciences, Addis Ababa University, Addis Ababa P.O. Box 9086, Ethiopia
*
Author to whom correspondence should be addressed.
Safety 2026, 12(4), 101; https://doi.org/10.3390/safety12040101
Submission received: 22 May 2026 / Revised: 24 July 2026 / Accepted: 27 July 2026 / Published: 3 August 2026

Abstract

Occupational health and safety (OHS) malpractices may increase the risk of occupational injuries and are a significant public health problem in the iron and steel industries, often leading to disability and death. Information on OHS practices related to occupational injuries in the iron and steel industries is limited in many countries. This study aimed to assess OHS practices in relation to occupational injuries among workers in the iron and steel industries in Tanzania. A cross-sectional study was conducted among 321 production line workers. Data were collected through interviews, using a structured OHS questionnaire and the modified International Labour Organization (ILO) injury assessment tool. A total of 209 workers had experienced an occupational injury in the past year. According to univariate regression analyses, the safety practice variables ‘safety inspections’ and ‘use of personal protective equipment’ were significantly associated with occupational injury. However, after adjusting for sociodemographic and organizational factors, including years of work experience, work section, daily working hours, and shift work, these associations were no longer statistically significant. Working in the rolling mill, having less than four years of work experience, working more than 10 h per day, and performing shift work were significant predictors of occupational injuries. These factors attenuated the associations between safety practices and occupational injuries. The severity of injuries was found to be related to the accessibility of PPE. The findings suggest that work experience and organizational characteristics play a critical role in shaping occupational injury risk, highlighting the need for multifaceted interventions that integrate effective safety practices, work experience and organizational measures to improve worker safety in Tanzania’s iron and steel industry.

1. Introduction

The iron and steel industry is among the most crucial global sectors, serving as a backbone for construction, infrastructure development, and manufacturing. Steel consumption is widely recognized as an indicator of economic growth, with the industry contributing to about US$8.2 trillion of the global economy, equivalent to 10.7% of the global GDP, and employing about 6 million people worldwide [1]. In Tanzania, this sector employs approximately 14,889 workers and continues to expand due to increasing demand driven by infrastructure development, industrial growth, and rapid urbanization [2].
The iron and steel industry is associated with a wide range of occupational hazards. Workers are exposed to risks such as loud noise, vibrations, extreme temperatures, working in confined spaces, slips, trips, and falls, falling objects, electric shock, burns from molten metal, unguarded machinery, fires, and explosions [3].
Occupational injuries remain a major public health concern worldwide. According to the International Labour Organization (ILO), an occupational injury refers to any personal injury, disease, or death resulting from an occupational accident [4]. A systematic review conducted across fifteen countries reported a pooled prevalence of 55% of occupational injuries among iron and steel workers [5], which is higher than estimates reported in other sectors, including small-scale industries in Sub-Saharan Africa, with a pooled prevalence of 53.2% [6].
The provision of a safe and healthy working environment is a fundamental right and a key principle in occupational health [7]. A safe and healthy working environment can be achieved if OHS measures are implemented effectively within the workplace. OHS practices encompass several interrelated components, including the presence of safety policies, use of personal protective equipment (PPE), regular safety inspections, risk assessment, health surveillance, and safety training programs [8].
Previous studies have demonstrated the importance of these components in reducing occupational injuries. For example, the availability and enforcement of OHS policies have been associated with improved safety outcomes and reduced injury rates [9]. Similarly, safety training and on-the-job education have been shown to significantly reduce occupational accidents by improving workers’ awareness and preventive behaviors [10,11]. Regular safety inspections play a critical role in identifying hazards and ensuring compliance with safety standards [12,13]. In addition, the consistent use of PPE has been reported to lower the risk of injuries in various industrial settings significantly [14,15,16]. Medical examinations, including pre-employment and periodic assessments, also contribute to early detection of health risks and support preventive strategies [17,18].
Although these studies highlight the importance of individual OHS components, most existing research has focused on specific aspects of OHS practices or on sectors other than the iron and steel industry [19]. In Tanzania, research on OHS practices remains scarce. Existing studies have primarily focused on general OHS conditions [20], and the few that have studied specific sectors such as construction and agriculture often reported low levels of OHS implementation [21,22]. A study conducted in a sugarcane factory examined selected OHS components and their relationship with occupational injuries, but did not comprehensively assess the relative contribution of different OHS practices [23].
Therefore, there is a need for comprehensive empirical evidence for a better understanding of how various OHS practices interact and contribute to the prevention of occupational injuries in the iron and steel industry. Such information is essential for designing effective workplace interventions and improving occupational safety in this high-risk sector. This study aimed to assess OHS practices and examine their association with occupational injuries among workers in the iron and steel industries in Tanzania.
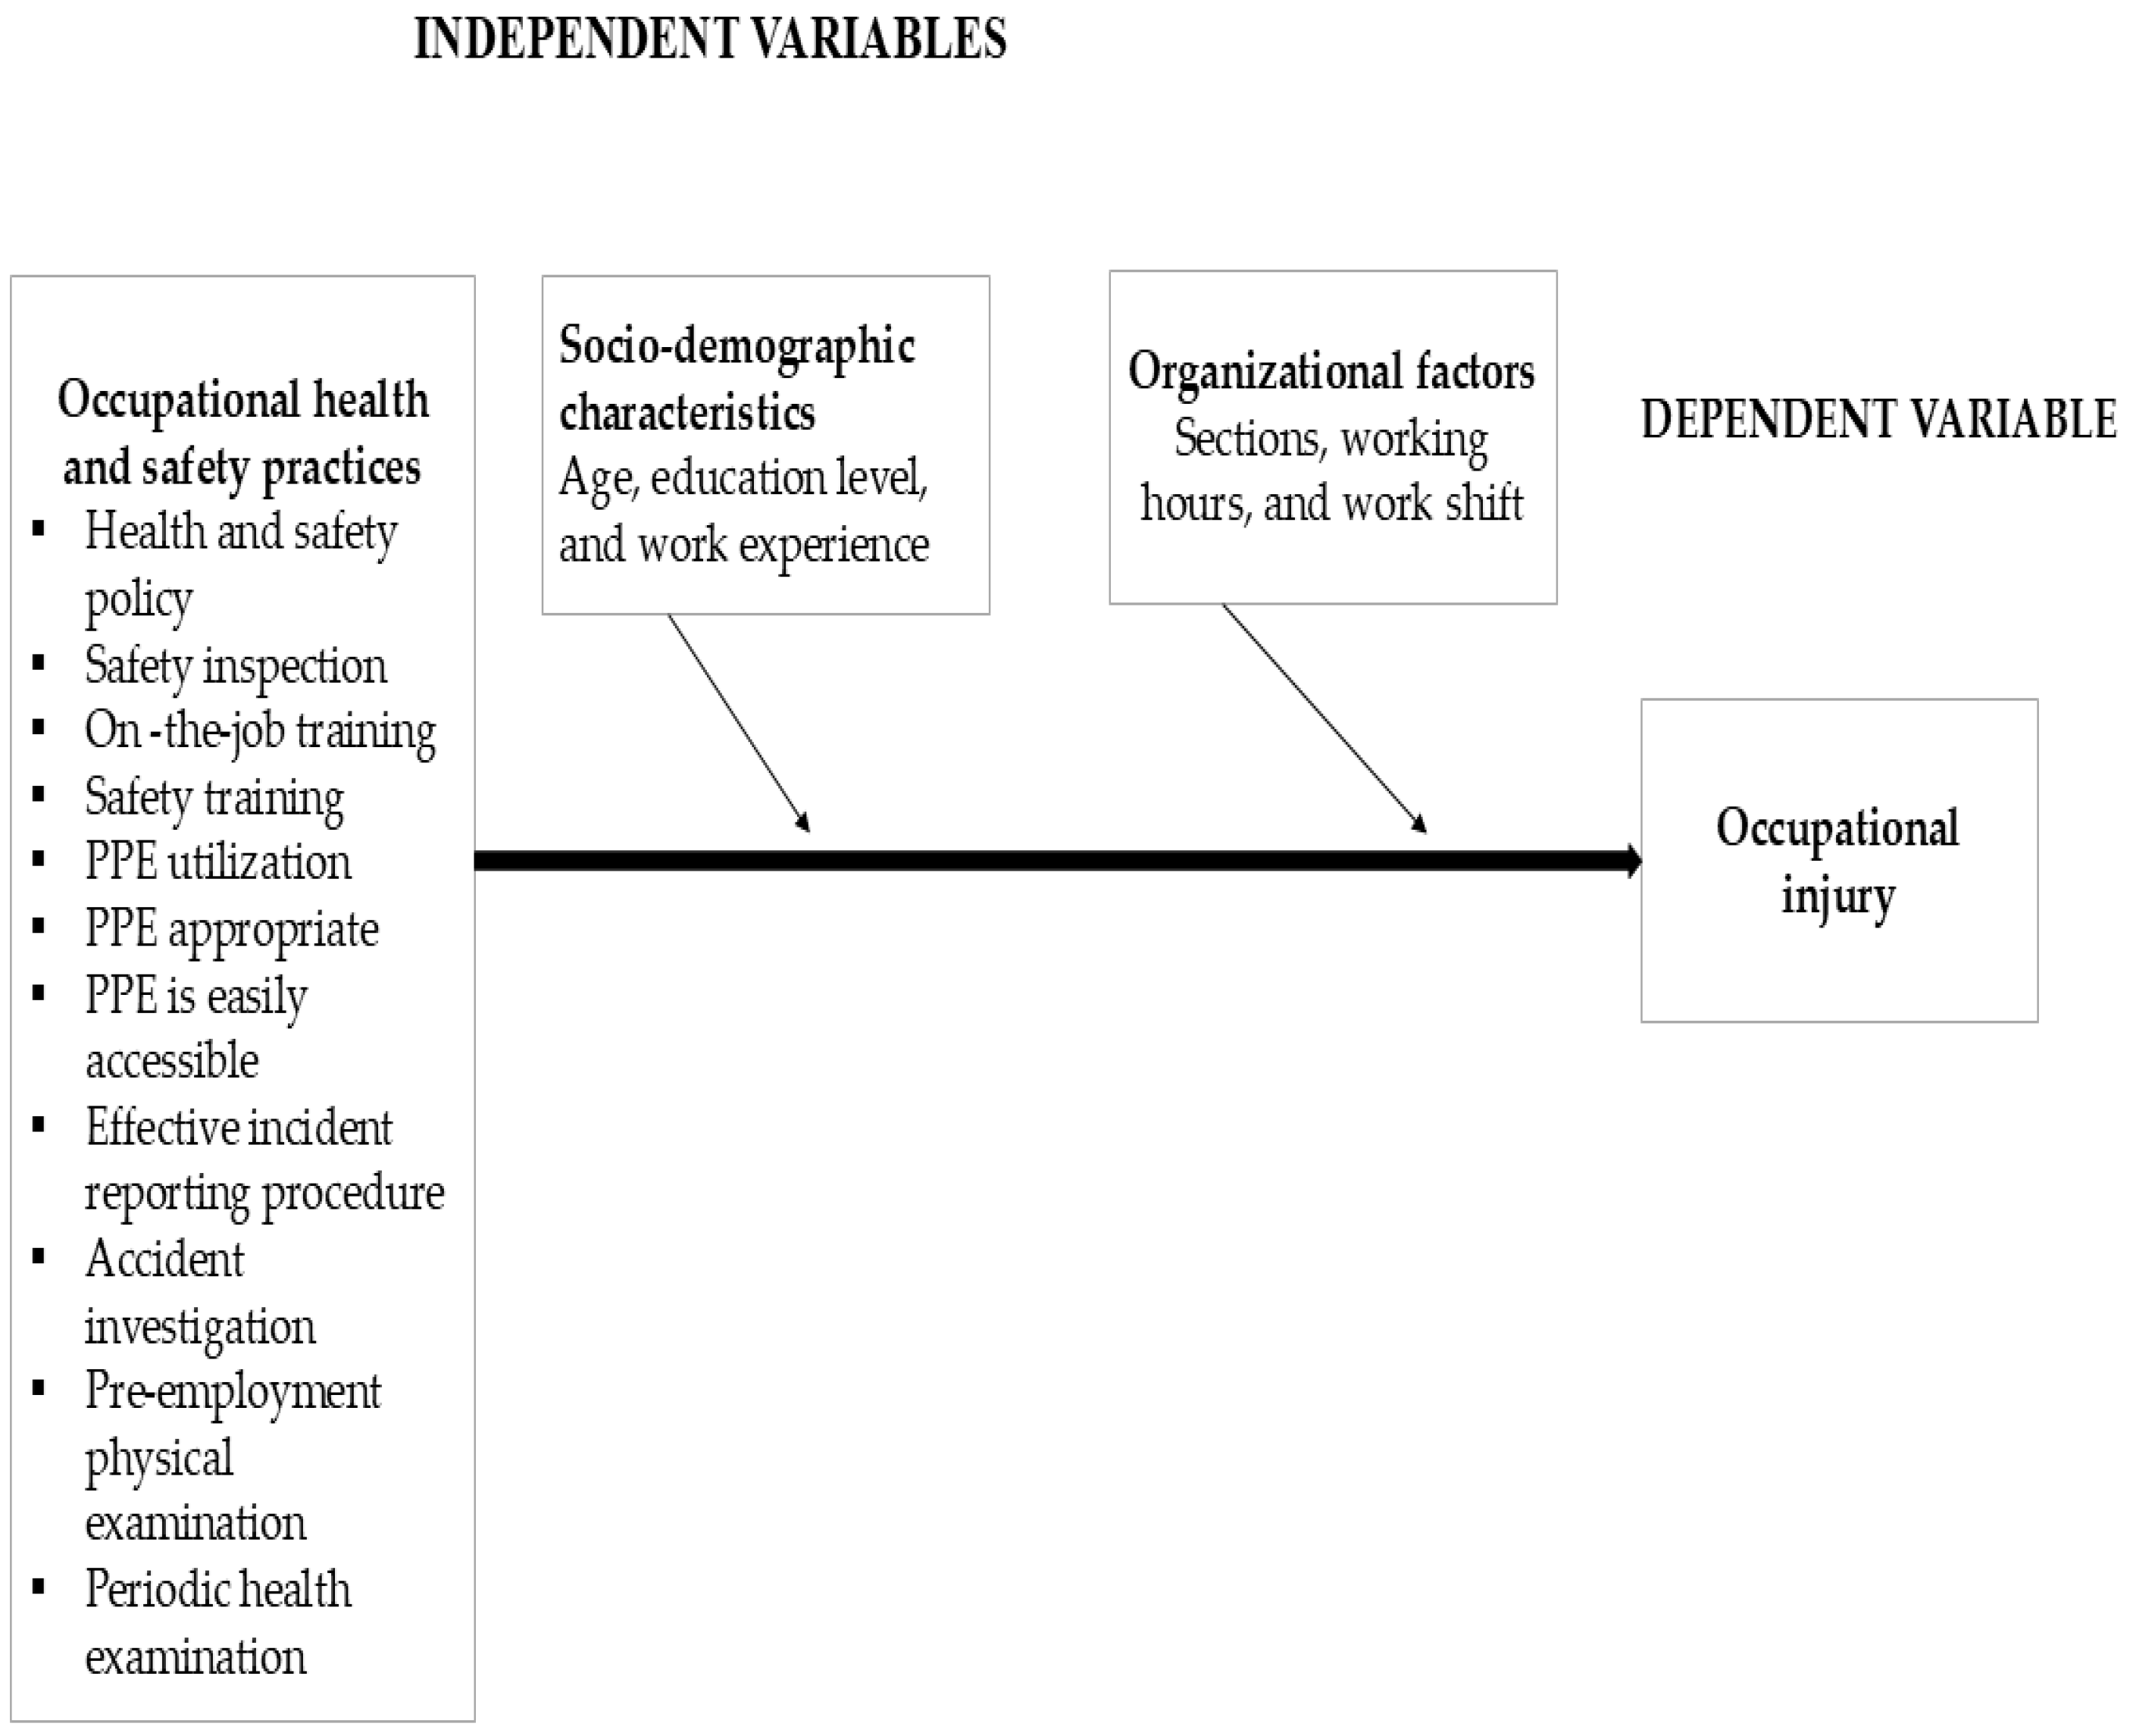
The conceptual framework of the study is shown in Figure 1. The figure shows the tentative relationship between the variables. Occupational injuries (dependent variable) might be influenced by OHS practices such as the implementation of health and safety policies, safety inspection, training, PPE use, incident reporting, accident investigation, pre-employment and periodic medical examination. However, the occurrence of occupational injuries may also be affected by socioeconomic and organizational factors (Figure 1).
This paper is organized as follows: Section 1 is the Introduction; Section 2 presents the materials and methods; Section 3 describes the results; Section 4 provides a discussion; and Section 5 concludes the study.

2. Materials and Methods

2.1. Study Setting and Design

This cross-sectional study was conducted from July 2022 to September 2023 in Dar es Salaam and the coastal (Pwani) regions of Tanzania. These two regions were selected due to the availability of a large number of iron and steel factories, relative to other regions of Tanzania. Four factories were randomly selected from a list of iron and steel industries provided by the Occupational Safety and Health Authority in Tanzania. Two industries were located in Dar es Salaam and two in the Coastal region. One industry initially hesitated to join the study, but finally decided to participate. This made the study period longer than originally planned. We do not know the reasons why that industry was reluctant to participate.

2.2. Sample Size

This study was part of a larger investigation concerning occupational injuries in the iron and steel industry. The sample size was determined using Open Epi software (Open Source Statistics for Public Health, Sullivan K.M., Emory University, 2007) for estimating a single population proportion. Assuming a prevalence of occupational injuries of 33% based on a previous study conducted in Addis Ababa, Ethiopia [24], a 95% confidence level, and a margin of error of 5%, the calculated sample size was 381. To reduce selection bias, four factories were randomly selected from a list of registered iron and steel factories obtained from the Tanzanian Occupational Safety and Health Authority (OSHA). The four selected factories have the following similarities: registered with the Tanzanian OSHA, more than 50 permanent employees, and similar steel production processes. They differ in their years of operation, production capacity, and workforce size. The manufacturing process in these factories was divided into two main, separate sections: the furnace and rolling mill sections. Details regarding the process are provided in a previous publication [25].
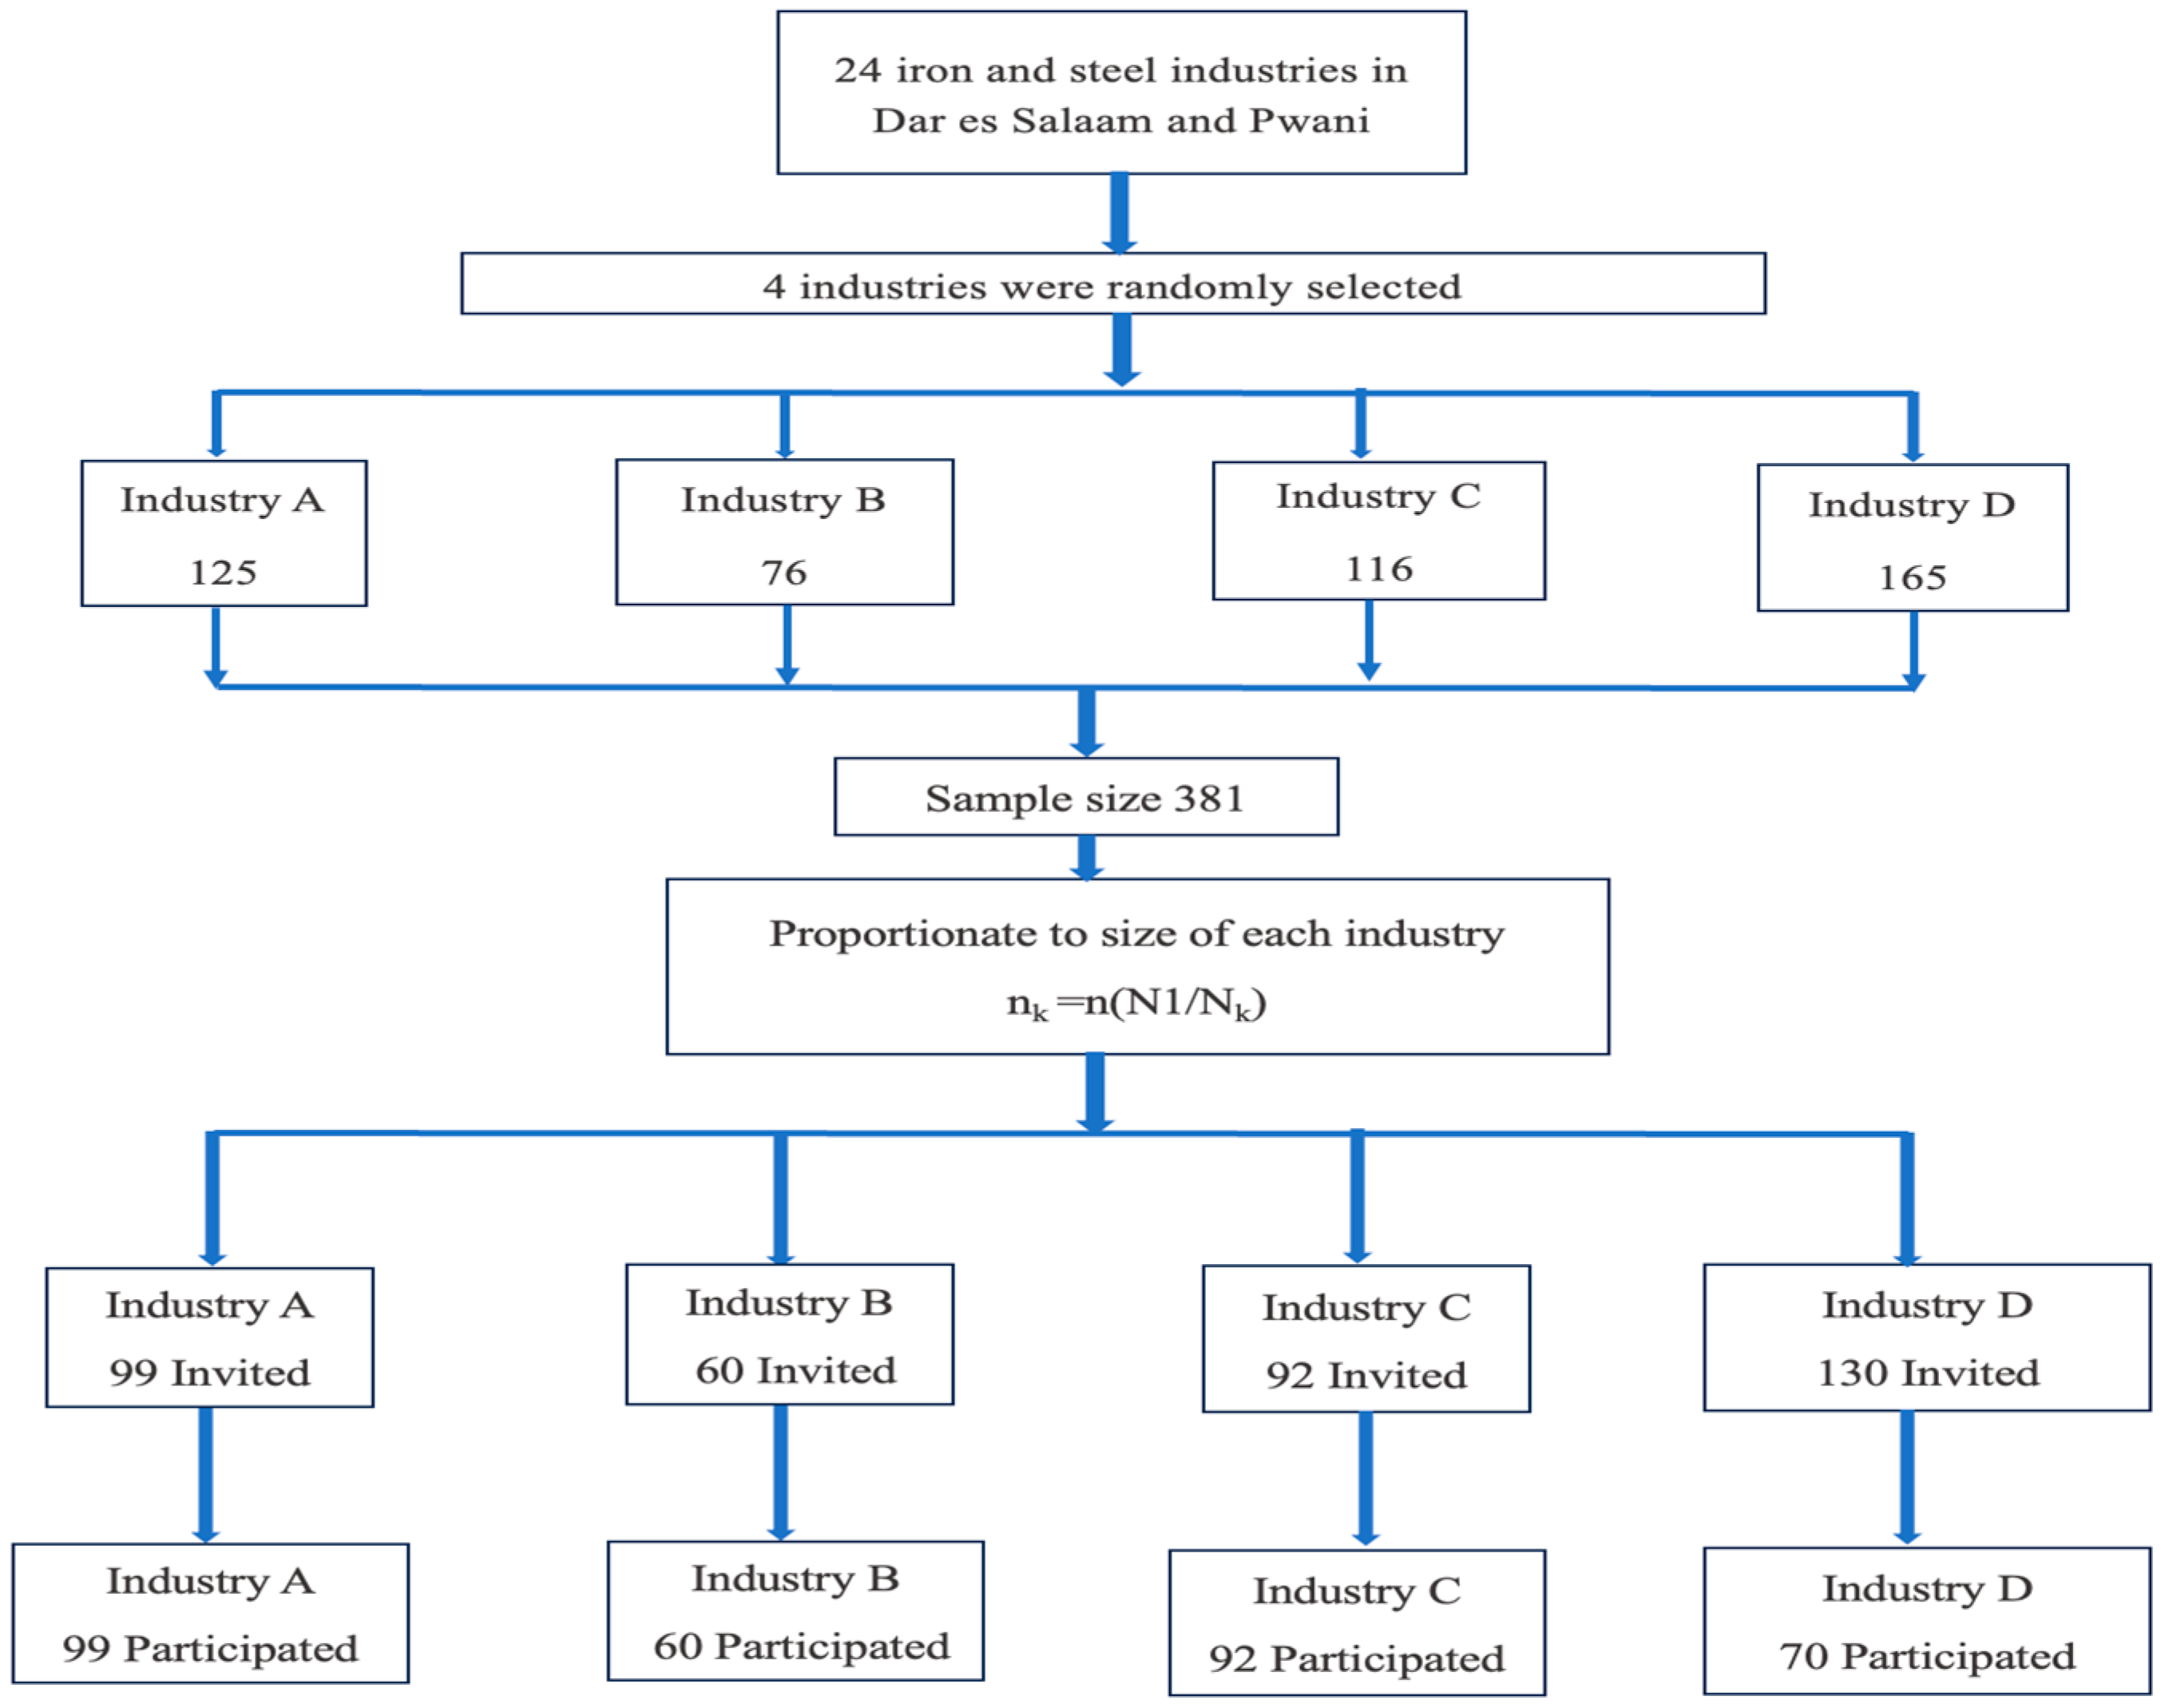
A total of 381 production line workers from four iron and steel factories were invited to participate in the study, with the sample proportional to the number of workers in the production line of each factory. Industry A had 125 workers in the production line, and we randomly selected 99 participants from this group. Similarly, industry B had 76 production workers, and 60 workers were randomly selected; industry C had 116 production workers, and 92 were randomly selected; and industry D had 165 workers, and 130 were randomly selected. Among the 381 selected, 321 participants provided informed consent to participate and were included in the final analysis (Figure 2). We do not know why some workers did not consent to participation in the study. However, this low response rate was only seen in industry D, which was also the industry that hesitated to participate.

2.3. Data Collection Tool and Procedures

A structured questionnaire modified from an ILO manual on methods for collecting occupational injuries statistics from household surveys and establishment surveys [4] was used to obtain information on occupational injuries. The structured OHS questionnaire was used to measure OHS practices. The questionnaire was originally in English and was translated into Swahili and subsequently translated back from Swahili to English. Before the actual data collection, a pre-test was conducted in 2022, where 20 workers from another factory not participating in the present study completed the questionnaire, and a few minor corrections were made afterwards. A few questions needed clarification, with more words included in the explanations. For instance, the question ‘Do you work shifts’ was changed to ‘Do you have a shift work schedule’. A research assistant with a bachelor’s degree in sociology, who had experience with data collection, was trained to collect the data by interviewing each worker. The data were collected by the principal investigator and the research assistant, and the interviews took place at the worksite, in a private room during working hours. The research assistant reported and discussed the data collected daily with the principal investigator throughout the data collection period.

2.4. Sociodemographic and Organizational Factors

The questionnaire included the following socio-demographic variables: age and education level. In addition, the workers were asked for their number of working years (1–4 years or above 4 years), working hours per day (≤10 h and above 10 h), shift work (daytime work only or work including night shifts) and work section.

2.5. Measurement of Occupational Injuries

The presence of occupational injuries in the past year among iron and steel industry workers was the outcome variable. Occupational injuries were specifically defined for the participants as all accidents that had caused a personal injury at the workplace or elsewhere, while the worker was carrying out business for the employer [4]. To be defined as an occupational injury, the injury must have caused the worker to be unable to work (incapacitated) for at least one day in addition to the day of the accident [4]. The following two questions were asked to identify occupational injuries:
(1)
Have you ever been injured in an occupational accident that occurred in the last 12 months?
(2)
Did any of the injuries you experienced in the last 12 months result in you being absent from work, or unable to work, for at least one day, apart from the day of the accident?
These questions were answered YES or NO. Both questions needed to be answered YES for the event to be registered as an occupational injury. In case of severity, we asked the worker to describe the number of workdays lost due to the most recent occupational injury. Injuries resulting in three or fewer days lost were classified as minor injuries, while those leading to more than three days lost were classified as serious injuries. This classification was based on definitions provided by the ILO and the Tanzania OSHA Act on accident notification and recording [9,25].

2.6. Measurement of Occupational Health and Safety Practices

The OHS practices were measured by using questions developed through an extensive review of relevant regulatory and empirical sources. These included the Tanzania Occupational Safety and Health Act of 2003 [26], a performance audit report on the management of OHS in Tanzania, the status of OHS and related challenges in the expanding economy of Tanzania [20], and a survey on the implementation of the OHS Act at an academic hospital in Johannesburg [27]. Based on this review, questions were formulated to capture key dimensions of OHS practice within the workplace. Respondents were asked the following questions: 1. Does your workplace have a written OHS policy? 2. Do safety officers and safety supervisors at your workplace carry out safety inspections at regular intervals to detect hazards? 3. Do you use PPE? 4. Is the use of PPE appropriate for your job task? 5. Is personal protective equipment easily accessible? PPE was defined as equipment used to prevent or minimize exposure to hazards. 6. Have you received any on-the- job training related to your job? 7. Did your employer provide you with comprehensive training on health and safety issues? 8. Do you have an effective accident reporting procedure that is known by all employees? 9. Are all accidents investigated in a timely manner to improve safety in the workplace? 10. Is a pre-employment physical examination offered by your employer? 11. Does your employer provide periodic health examinations? All questions were answered YES or NO. The items of the questionnaire used were reliably tested, with a Cronbach’s alpha of 0.850.

2.7. Data Analysis

The collected data were cleaned by checking for duplicates, missing values, and out-of-range values using frequency distributions, descriptive statistics, and cross-tabulations. Any discrepancies were corrected, followed by coding and analysis using IBM Statistical Package for Social Sciences (SPSS), version 27. Continuous variables were described using mean and standard deviation (mean; SD), and categorical variables were described based on proportion (%). Chi-square tests were used for comparisons of categorical variables. The significance level was set to be lower than or equal to 0.05. Binary and multivariate logistic regression analyses were performed to assess the potential determinants of occupational injuries, and adjustments were performed for age, education, work experience, work section, daily working hours, and shift work.

2.8. Ethics

Ethical approval was obtained from the Muhimbili University of Health and Allied Science institutional review board on 31 March 2022 with approval number MUHAS-REC-03-2022-1061. Permission letters were provided by all managers of the selected factories and were distributed to the workers. All participants gave their written consent before any interviews were performed, and confidentiality regarding their information was maintained. This study was performed in accordance with the Declaration of Helsinki.

3. Results

3.1. Description of Study Participants

Of the 381 invited workers, 321 (84%) participated in the study. All participants were male; no female workers were engaged in any of the production line activities during the study period. The mean age of the participants was 32 (±8) years. Most workers had completed secondary education (53%). The majority work in rolling mills (56.7). About (76.3%) had less than or equal to four working years. Many of the iron- and steelworkers (76%) worked for more than 10 h per day, and 42.7% of the workers had a daytime shift work schedule. This study is a part of a larger project, and details regarding the study population have been described in a previous paper about occupational injury prevalence [26]. The prevalence of occupational injuries was 209 (65.1%) (Table 1).

3.2. Occupational Injuries and Safety Practices

A total of 209 (65.1%) had experienced injuries that restricted them from working for at least 1 day, fulfilling the definition of occupational injury. Comparing safety practices among workers who had experienced an occupational injury in the past year and those who had not, univariate regression analyses showed that failure of safety officers and safety supervisors to conduct regular safety inspections to identify hazards (OR = 1.6, 95% CI: 1.02–2.59, p = 0.040) and lack of PPE use (OR = 1.8, 95% CI: 1.08–2.83, p = 0.021) were significantly associated with occupational injury (Table 2). Adjusting for the sociodemographic variables age and education did not change these results, but when adjusting for working years and the organizational variables (working hours, work section, and shift work), the associations between safety practices and injuries were no longer statistically significant. After adjustment, working years (AOR = 1.98, 95% CI: 1.05–3.73, p = 0.035), working hours (AOR = 2.7, 95% CI: 1.52–4.83, p < 0.001), and shift work (AOR = 1.87, 95% CI: 1.06–3.27, p = 0.030) became independent predictors and modified the effect of safety inspection and PPE use on occupational injuries (Table 2).

3.3. Occupational Health and Safety Practices

Overall, 65.4% of the workers reported that their workplace did not have a written OHS policy (Table 1). In addition, only 58.3% of the workers reported using PPE. Most respondents (78.8%) indicated that an effective incident reporting procedure was in place and known to all employees. Among the respondents, 76.9% reported that their employer did not provide a pre-employment physical examination, while 94.7% reported that no periodic health examinations were offered.

3.4. Occupational Injury Severity and Safety Practices

Among the 209 workers who had experienced occupational injuries, 135 (64%) reported minor injuries (injuries resulting in three or fewer workdays lost), and 74 (33.4%) reported serious injuries (with more than three days lost). Based on a univariate analysis, we found an association between the severity of the injury and the positive answers to this question on safety practice ‘Is the use of PPE appropriate for your job task’ (Table 3). This finding was also significant after adjusting for age group, education level, working years, working hours, section, and work shift.

4. Discussion

This study aimed to assess OHS practices in relation to occupational injuries among workers in the iron and steel industry. The findings revealed inadequate implementation of OHS practices in this sector. The safety practice variables ‘safety inspections’ and ‘use of personal protective equipment’ were significantly associated with occupational injury in univariate analyses. However, after adjusting for work experience and the organizational factors ‘work section’, ‘daily working hours’, and ‘shift work’, these associations were no longer statistically significant. Injury severity was associated with the variable appropriateness of PPE.
We found that about 65.4% of workers reported the absence of a written OHS policy in their workplace. Although Tanzania’s Occupational Health and Safety Act No. 5 of 2003 in Section 96, states that “Every employer who has more than four employee in his employment in any factory shall have the duty to prepare a written policy on the protection of health and safety of employees and description of the organization for the implementing the policy and also require to distribute the copy of policy and guideline to all employees” [26], this was not implemented. OHS policy is a statement written by an employer describing the employer’s commitment to protecting the health and safety of employees and the public. The assessed iron and steel factories of the present study failed to implement this requirement. This failure undermines the efforts to uphold general OHS standards at the workplace. An effective OHS policy is essential as it informs the workers about potential hazards and outlines preventive measures to reduce the risk of injury. It also ensures that employees receive proper training, safety equipment, and other resources necessary for safe work practices. The absence of an OHS policy may significantly increase the risk of occupational accidents and injuries to workers, while also reflecting weak law enforcement. However, in the present study, no clear relationship was found between having a safety policy and occupational injury. This was unexpected, and we do not know the reason for this finding. For instance, in a study conducted in two Canadian provinces, where they reported that 50.3% of workers who experienced policy and procedure vulnerability reported a physical injury in the preceding 12 months compared with just 10.3% of those who were not vulnerable and had a supportive supervisor [13].
Regarding safety inspection, this study found that 59.5% of workers reported that safety officers and safety supervisors did not carry out safety inspections at regular intervals to detect hazards, and among them, 70.4% had been injured. These findings are consistent with those reported in a study conducted in South Africa, which revealed that failures in supervision, including the failure to ensure routine inspections, indicate an ineffective safety culture within the railway industry and may contribute to increased accident rates [12]. In many workplaces, internal inspections are not performed until after an accident has occurred, and it makes them reactive rather than preventive. In some industries, inspections are conducted only a few days before OSHA visits, primarily for compliance purposes. However, inspections should be proactive in nature, focusing on the prevention of accidents and occupational illnesses, as well as on promoting effective OSH management practices [28]. When inspections are not conducted effectively, workplace hazards may remain undetected, necessary corrective action may be delayed, and the risk of occupational injury may increase. Therefore, to reduce accident rates, industries need to shift from a reactive approach to a proactive safety culture. By doing so, they can significantly enhance workplace safety, protect their employees, and reduce the likelihood of costly accidents and regulatory penalties.
The majority of workers who did not use PPE had experienced injuries relative to their counterparts who used PPE. This finding is consistent with previous empirical evidence, which collectively reported that inadequate utilization of PPE constitutes a risk factor for occupational injuries [5,15,29]. Among the factors reported by workers as barriers to PPE utilization was limited accessibility. About 63.1% of participants reported that PPE was not easily accessible and consequently did not use it. This finding aligns with a study conducted in Ethiopia, where 40.9% of non-users cited unavailability as the reason for not wearing PPE [14]. Furthermore, among workers who reported the PPE as inappropriate for their job task, about 82.1% did not use PPE. This result is consistent with a study from Egypt, which reported that 40.6% of workers reported not using PPE, and among their reasons was the poor fit of the PPE [16]. For PPEs to be effective in accident prevention, they have to be readily available, accessible, and appropriately fitted.
Regarding training, about 45.8% of the respondents in our study stated that their employer did not provide comprehensive training on health and safety issues, and 92 (62.7%) of them had experienced an occupational injury. Our findings are supported by a qualitative investigation examining occupational injury causes and preventive countermeasures in manufacturing companies conducted in Iran. This Iranian study reported that a lack of safety training courses can contribute to occupational injuries [30]. Likewise, in a study conducted in the USA’s dairy product manufacturing industry, about 24% of the respondents reported that lack of training or knowledge is a reason for the high number of occupational injuries in their workplace [31]. Safety training is a very important aspect of a workplace, since it enables the worker to identify occupational hazards and increase their awareness about adverse health effects from hazardous substances and makes the worker eager to adhere to the safety rules and regulations available in the workplace, such as proper use of PPE, and thus ultimately decreasing the risk of occupational injury [11].
Pre-employment and periodic physical examination are neglected in the iron and steel industry, with 76.9% of the respondents reporting that their employer did not offer a pre-employment physical examination, and 94.7% reporting that their employer did not provide a periodic health examination. Pre-employment medical examinations are essential for evaluating a worker’s capacity to perform job tasks without posing a risk to their own or others’ health [17]. The absence of such assessments may result in the recruitment of employees with pre-existing medical conditions, who may then be exposed to multiple hazardous substances typical in the iron and steel industries, potentially exacerbating their conditions. Furthermore, the lack of pre-employment examinations can complicate compensation processes, as it becomes difficult to establish causality or provide evidence that a particular condition is work-related. One of the barriers to pre-employment and periodic examinations was their high costs [18].
Workers in the rolling mill section were more affected by occupational injuries compared with those in the furnace section, and this can be due to the moving rollers and conveyors, sharp objects, and physically demanding tasks, which increase the risk of occupational injuries. The finding is consistent with a study conducted in Bishoftu, Ethiopia, that reported a 12-month prevalence of 54.2% among workers in a rolling mill [32]. In our present study, we found that work section was initially associated with occupational injuries in the univariate analysis, but this association disappeared after adjustment for work experience, working hours, and shift work.
We found that work experience, working hours, and shift work were significantly associated with occupational injury and attenuated the effect of not using PPE and the failure of safety officers and safety supervisors to carry out safety inspections. Less experienced workers may have a shortage of skills in hazard identification or proper use of PPE and have less knowledge of safety procedures. This finding is consistent with those from other studies conducted in industrial settings, which found that work experience is the main determinant of occupational injuries [33,34,35,36]. Furthermore, a previous study from the USA revealed that workers with more job experience have higher levels of perceived health and safety skills [34].
Similarly, exposure to long working hours may increase fatigue, which is connected to reduced alertness, impaired decision-making, and diminished concentration and memory. Long working hours may also promote risk-taking behavior and ultimately reduce adherence to safety practices [37], thereby increasing the risk of occupational injuries at the workplace. This finding has been reported in other studies demonstrating the impact of long working hours on occupational injuries [38,39]. Furthermore, shift work, particularly night shifts, can disrupt circadian rhythms, impair sleep quality, and increase fatigue. These effects may reduce the concentration, alertness, cognitive performance, and reaction time of the workers, thereby increasing the risk of occupational accidents and injuries. Our present finding is in line with a systematic review and meta-analysis, which found that night shift work has a higher impact than other factors in the occurrence of occupational injuries in the iron and steel industry [5]. Although non-use of PPE and the failure of safety officers and supervisors to carry out safety inspections were not statistically significant after adjustment for working hours, their effects on occupational injuries should not be overlooked. Their odds ratios remained above 1, indicating that they may still function as risk factors for occupational injuries. Therefore, these findings suggest that effective occupational injury prevention strategies should integrate both safety practices and work experience programs, such as comprehensive orientation, mentoring, and training to enhance familiarity with the machines and tools in use, and their defects, as well as awareness of surrounding hazards. In addition, it is also important to regulate work schedules to reduce the occurrence of long working hours and shift work.
Regarding the severity of occupational injuries and presence of safety practices, our findings showed that workers who reported that their PPE was appropriate for their task were more affected by serious injuries and less by minor injuries, with the result being statistically significant. These findings are different from results in a review study, which showed that appropriate PPE fit reduces the risk of occupational injuries [40]. This can be explained by the fact that the iron and steel industry is a hazardous industry wherein accident-related hazards are prevalent. Therefore, workers can be given the appropriate PPE for some risk factors but not for others, leading to inconsistent reporting on this question. On the other hand, the results might also mean that the use of PPE and a lack of training on their proper use can affect the occurrence and severity of occupational injuries [15].

The Strengths and Limitations of the Study

This is the first study conducted in Tanzania assessing OHS practices and occupational injuries in the iron and steel industry. The response rate in this study was high, as the workers were generally willing to provide information. However, several limitations should be acknowledged. The cross-sectional design prevents the establishment of causal relationships between OHS practices and occupational injuries, as both exposure and outcome were assessed at a single point in time. Consequently, the observed associations should be interpreted with caution because the temporal sequence between OHS practices and injury occurrence cannot be established. It is possible that workers who have experienced occupational injuries are more aware of workplace safety measures or reported greater adherence to practices such as personal protective equipment use, resulting in a potential reverse association. Future studies should adopt longitudinal designs to better capture temporal relationships between OHS practices and occupational injury occurrence. Also, future studies should use both quantitative and qualitative research methods to provide deeper insight into the underlying reasons for the interaction between OHS practices and occupational injuries. Additionally, the data in this study were collected through self-reports, which may introduce information biases due to recall inaccuracies or misreporting. However, this risk was mitigated by using a validated tool for obtaining injury information and limiting the recall period to the past year. Social desirability bias is another potential concern, as the workers might have hesitated to provide honest responses due to fear of management repercussions. To minimize this, interviews were conducted in a private setting, and the participants were assured of confidentiality and anonymity.
This study was conducted in four factories across two regions in Tanzania. It is likely that these factories are representative of the iron and steel industry in the country, although this cannot be confirmed with certainty. Therefore, one should be careful when generalizing the findings to other geographical settings, particularly given the variation in OHS policies, regulations, and practices across countries. When interpreting the transferability of our findings, one may, for instance, also consider differences in legislation. In our study, the working hours variable reflected the actual hours reported by participants. Therefore, our findings should be interpreted within the context of actual workplace practices rather than statutory working hours provisions. Nevertheless, similar findings might be observed in comparable factory sites in other low- and middle-income countries.

5. Conclusions

This study revealed inadequate OHS practices in the iron and steel industry. Work experience, working hours, and shift work were found to be predictors of occupational injuries in Tanzania’s iron and steel industry and were found to attenuate the associations between safety inspections, non-use of PPE, and occupational injuries. The severity of injuries was related to the accessibility of PPE. These findings indicate the need for comprehensive preventive strategies that integrate both safety practices and work experience programs and the regulation of working hours and work schedules to improve the prevention of occupational injuries.

Author Contributions

S.S. conceived the study, collected data, conducted data analysis, and wrote the first draft of the manuscript. S.H.M. conceived the study and reviewed the manuscript. W.D., S.H.M. and B.E.M. participated in the data analysis and reviewed the manuscript. All authors have read and agreed to the published version of the manuscript.

Funding

This research was funded by NORAD (Norwegian Agency for Development Cooperation) through the NORHED program (Norwegian Program for Capacity Development in Higher Education and Research for Development) via the NORHED II SAFE WORKERS PROJECT, no. 69181.

Institutional Review Board Statement

This study was conducted in accordance with the guidelines of the Declaration of Helsinki and was approved by the Publications Committee of Muhimbili University of Health and Allied Sciences (approval number MUHAS-REC-03-2022-1061; 31 March 2022).

Informed Consent Statement

All the participants were given both oral and written information about the study and gave their written, informed consent for participation in the study before their interview was conducted.

Data Availability Statement

The data presented in this study are available on request from the corresponding author due to restrictions from the ethical committee.

Acknowledgments

We are most grateful to Matiku and Materu from OSHA for their invaluable support and cooperation. We would like to sincerely thank the management team, health and safety officers, and workers who consented to participate in this study.

Conflicts of Interest

The authors declare no conflicts of interest. The study received funding from NORAD, but the funder was not involved in the study design, collection, analysis, interpretation of data, the writing of this article, or the decision to submit it for publication.

Abbreviations

The following abbreviations are used in this manuscript:
GDPGross Domestic Product
ILOInternational Labour Organization
OHSOccupational Health and Safety
OSHAOccupational Safety and Health Authority
WCFWorker’s Compensation Fund

References

  1. OECD. OECD Steel Outlook 2025. Available online: https://www.oecd.org/en/publications/oecd-steel-outlook-2025_28b61a5e-en.html (accessed on 25 February 2026).
  2. National Bureau of Statistics (NBS); Ministry of Industry, Trade and Industry (MITI). The 2013 Census of Industrial Production: Summary Report. Dar es Salaam, Tanzania. Available online: https://www.nbs.go.tz/uploads/statistics/documents/en-1705493816-Census_of_Industrial_Production_2013-Summary_Report.pdf (accessed on 25 February 2026).
  3. International Labour Organisation; Sectoral Activities Programme. Code of Practice on Safety and Health in the Iron and Steel Industry: Meeting of Experts to Develop a Revised Code of Practice on Safety and Health in the Iron and Steel Industry, Geneva; International Labour Office: Geneva, Switzerland, 2005. [Google Scholar]
  4. Taswell, K.; Wingfield-Digby, P. Occupational Injuries Statistics from Household Surveys and Establishment Surveys: An ILO Manual on Methods; International Labour Office: Geneva, Switzerland, 2008; p. 27. [Google Scholar]
  5. Shabani, S.; Mamuya, S.H.; Moen, B.E. The Prevalence of Occupational Injuries and Associated Risk Factors among Workers in the Iron and Steel Industries: A Systematic Review and Meta-Analysis. BMC Public Health 2024, 24, 2602. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Atalay, Y.A.; Gebeyehu, N.A.; Gelaw, K.A. Prevalence and Determinants of Occupational Injuries among Small-Scale Industry Workers in Sub-Saharan Africa. A Systematic Review and Meta-Analysis. Development 2023, 2, 3. [Google Scholar]
  7. International Labour Organization (ILO). A Safe and Healthy Working Environment Is a Fundamental Principle and Right at Work. Available online: https://www.ilo.org/topics-and-sectors/safety-and-health-work/safe-and-healthy-working-environment-fundamental-principle-and-right-work#:~:text=At%20its%20110th%20Session%20in,safety%20and%20health%20management%20system (accessed on 27 January 2026).
  8. Alli, B.O. Fundamental Principles of Occupational Health and Safety; International Labour Office: Geneva, Switzerland, 2001. [Google Scholar]
  9. Ehnes, H.; Niu, S. Improvement of National Reporting, Data Collection, and Analysis of Occupational Accidents and Diseases; International Labour Office: Geneva, Switzerland, 2012. [Google Scholar]
  10. Jayadi, Y.D.; Lestari, F.; Tejamaya, M.; Prasetyo, S.; Fikawati, S.; Astono, S.; Mayawati, H.; Noor, I.H.; Modjo, R.; Dharmayanti, I. Occupational Safety and Health Education for Reducing Workplace Accidents in Oil Palm Plantations. Int. J. Occup. Saf. Health 2025, 15, 361–369. [Google Scholar] [CrossRef] [Scilit]
  11. Yu, I.T.S.; Yu, W.; Li, Z.; Qiu, H.; Wan, S.; Xie, S.; Wang, X. Effectiveness of Participatory Training in Preventing Accidental Occupational Injuries: A Randomized-Controlled Trial in China. Scand. J. Work Environ. Health 2017, 43, 226–233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Tau, S. Analyzing the Impact That Lack of Supervision Has on Safety Culture and Accident Rates as a Proactive Approach to Curbing the South African Railway Industry’s High Incident Occurrence Rate. In Advances in Social & Occupational Ergonomics: Proceedings of the AHFE 2016 International Conference on Social and Occupational Ergonomics, 27–31 July 2016, Lake Buena Vista, FL, USA; Springer: Cham, Switzerland, 2016; pp. 189–197. [Google Scholar]
  13. Yanar, B.; Lay, M.; Smith, P.M. The Interplay between Supervisor Safety Support and Occupational Health and Safety Vulnerability on Work Injury. Saf. Health Work 2019, 10, 172–179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Teym, A.; Zeleke, T.K. Utilization of Personal Protective Equipment and Its Key Factors among WA Oil Factory Workers in Debre Markos Town, Ethiopia. Front. Public Health 2025, 13, 1529436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Malta, G.; Matera, S.; Plescia, F.; Calascibetta, A.; Argo, A.; Cannizzaro, E. Occupational Accidents and the Use of PPE: A Global Meta-Analysis. Front. Public Health 2024, 12, 1368991. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Sehsah, R.; El-Gilany, A.-H.; Ibrahim, A.M. Personal Protective Equipment (PPE) Use and Its Relation to Accidents among Construction Workers. Med. Lav. 2020, 111, 285. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Palmer, K.T.; Cox, R.A.F.; Brown, I. Fitness for Work: The Medical Aspects, 4th ed.; Oxford University Press: Oxford, UK, 2007. [Google Scholar]
  18. Sadaf, M.; Kashani, M.M.; Saberi, H.R.; Akbari, H.; Bidgoli, S.D.; Hannani, M. Investigating and Prioritizing of the Barriers of Performing Periodic Occupational Examinations in Industries of Kashan City in 2019. Int. Arch. Health Sci. 2021, 8, 122–126. [Google Scholar] [CrossRef] [Scilit]
  19. Ajmal, M.A.; Isha, A.N.S.; Nordin, S. A Safety Management Practices and Occupational Health and Safety Performance: An Empirical Review. Jinnah Bus. Res. Cent. Cap. Univ. Sci. Technol. Islam. 2021, 9, 15–33. [Google Scholar] [CrossRef] [Scilit]
  20. Mrema, E.J.; Ngowi, A.V. Status of Occupational Health and Safety and Related Challenges in Expanding Economy of Tanzania. Ann. Glob. Health 2015, 81, 538–547. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Gervas, A.; Torm, N.; Kinyondo, G. Health and Safety Compliance in Tanzania: Regulatory Impediments in the Construction Sector. Afr. Stud. Q. 2023, 21, 29–48. [Google Scholar] [CrossRef] [Scilit]
  22. Mhando, Y.B. Factors of Inefficient Use of Personal Protective Equipment: A Survey of Construction Workers at Arusha Urban in Tanzania. J. Constr. Eng. Manag. Innov. 2021, 4, 1–11. [Google Scholar] [CrossRef] [Scilit]
  23. Mwera, I.C.; Sichalwe, M.M.; Mamuya, S.H.; Mwelange, L.P. Work-Related Injuries and Occupational Safety Practices among Sugar Factory Workers in Tanzania: A Cross-Sectional Study. Sage Open Med. 2025, 13, 20503121251385676. [Google Scholar] [CrossRef] [Scilit]
  24. Kifle, M.; Engdaw, D.; Alemu, K.; Sharma, H.R.; Amsalu, S.; Feleke, A.; Worku, W. Work Related Injuries and Associated Risk Factors among Iron and Steel Industries Workers in Addis Ababa, Ethiopia. Saf. Sci. 2014, 63, 211–216. [Google Scholar] [CrossRef] [Scilit]
  25. Shabani, S.; Moen, B.E.; Deressa, W.; Mamuya, S.H. Prevalence of Occupational Injuries among Workers in the Iron and Steel Industries in Tanzania. Ann. Glob. Health 2025, 91, 9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. The United Republic of Tanzania. Office of the Solicitior General e-Library. The Occupational Health and Safety Act. Available online: https://elibrary.osg.go.tz/items/6c524261-4e5a-44ea-bced-167a6a72acda (accessed on 24 July 2026).
  27. Foromo, M.R.; Chabeli, M.; Satekge, M.M. Survey on the Implementation of the Occupational Health and Safety Act at an Academic Hospital in Johannesburg. Curationis 2016, 39, e1–e10. [Google Scholar] [CrossRef] [Scilit]
  28. International Labour Office. The Inspection of Occupational Safety and Health in Ports A Review of Existing Guidance and Practice. Available online: https://www.ilo.org/sites/default/files/wcmsp5/groups/public/@ed_dialogue/@sector/documents/publication/wcms_161219.pdf (accessed on 24 July 2026).
  29. Dodoo, J.E.; Al-Samarraie, H. A Systematic Review of Factors Leading to Occupational Injuries and Fatalities. J. Public Health 2023, 31, 99–113. [Google Scholar]
  30. Ghahramani, A.; Amirbahmani, A. A Qualitative Investigation to Discover Causes of Occupational Injuries and Preventive Countermeasures in Manufacturing Companies. Heliyon 2022, 8, e10501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Van Derlyke, P.; Marin, L.S.; Zreiqat, M. Discrepancies between Implementation and Perceived Effectiveness of Leading Safety Indicators in the US Dairy Product Manufacturing Industry. Saf. Health Work 2022, 13, 343–349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Woldeyes, B. Factors Influencing Occupational Injuries in Steely Rolling Mill Industry PLC, Bishoftu, Ethiopia. Master’s Thesis, Addis Ababa University, Addis Ababa, Ethiopia, 2020. [Google Scholar]
  33. Bena, A.; Giraudo, M.; Leombruni, R.; Costa, G. Job Tenure and Work Injuries: A Multivariate Analysis of the Relation with Previous Experience and Differences by Age. BMC Public Health 2013, 13, 869. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Haas, E.J.; Eiter, B.; Hoebbel, C.; Ryan, M.E. The Impact of Job, Site, and Industry Experience on Worker Health and Safety. Safety 2019, 5, 16. [Google Scholar] [CrossRef] [Scilit]
  35. Obeidat, M.S.; Dweiri, H.Q.; Smadi, H.J. Unveiling Workplace Safety and Health Empowerment: Unraveling the Key Elements Influencing Occupational Injuries. J. Saf. Res. 2024, 91, 126–135. [Google Scholar] [CrossRef] [Scilit]
  36. Nkomo, H.; Niranjan, I.; Reddy, P. Effectiveness of Health and Safety Training in Reducing Occupational Injuries among Harvesting Forestry Contractors in KwaZulu-Natal. Workplace Health Saf. 2018, 66, 499–507. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Jafarizaveh, M.; Jafarizadeh, R.; Esmaili, M.; Tabrizi, A. The Impact of Occupational Fatigue on Safety and Health Performance in the Porcelain Manufacturing Industry: An Analysis Using the ELMERI Index. Dialogues Health 2026, 8, 100283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Salminen, S. Long Working Hours and Shift Work as Risk Factors for Occupational Injury. Ergon. Open J. 2016, 9, 15–26. [Google Scholar] [CrossRef] [Scilit]
  39. Friedman, L.S.; Almberg, K.S.; Cohen, R.A. Injuries Associated with Long Working Hours among Employees in the US Mining Industry: Risk Factors and Adverse Outcomes. Occup. Environ. Med. 2019, 76, 389–395. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Santos, W.; Lorente, A.; Rojas, C.; Mariscal, G.; Lorente, R. Impact of Personal Protective Equipment in Preventing Occupational Injuries: A Systematic Review and Meta-Analysis. Front. Public Health 2025, 13, 1720363. [Google Scholar] [CrossRef] [Scilit]
Figure 1. Conceptual framework of occupational health and safety practices related to occupational injuries.
Safety 12 00101 g001
Figure 2. Sampling strategy and recruitment.
Safety 12 00101 g002
Table 1. Occupational health and safety practices among workers in the production line (n = 321).
Safety Practice VariableFrequencyPercent
Does your workplace have a written occupational health and safety policy?
Yes11134.6
No21065.4
Do safety officers and safety supervisors at your workplace carry out safety inspections at regular intervals to detect hazards?
Yes13040.5
No19159.5
Do you use personal protective equipment (PPE)?
Yes18758.3
No13441.7
Is the use of personal protective equipment appropriate for your job task?
Yes13843
No18357
Is personal protective equipment easily accessible at your workplace?
Yes15347.7
No16852.3
Have you received any on-the-job training related to your job?
Yes20262.9
No11937.1
Has your employer provided you with comprehensive training on health and safety issues?
Yes17454.2
No14745.8
Do you have effective accident reporting procedures at your workplace that are known for all employees?
Yes25378.8
No6821.2
Are all accidents at your workplace investigated in a timely
manner to improve safety?
Yes25178.2
No7021.8
Does your employer offer pre-employment physical examinations?
Yes7423.1
No24776.9
Does your employer provide periodic health examinations?
Yes175.3
No30494.7
Table 2. Logistic regression on occupational injury and occupational health safety practices among workers in the production line (n = 321).
VariablesOccupational InjuryOR (95%CI)p-ValueAOR (95%CI)p-Value
YesNo
Safety practice variablesno (%)no (%)
Does your workplace have a written occupational health and safety policy?
Yes73 (65.8)38 (34.2)ref -
No136 (64.8)74 (35.2)0.96 (0.59–1.55)0.858-
Do safety officers and safety supervisors carry out safety inspections at regular intervals to detect hazards?
Yes76 (56.8)54 (43.2)ref ref
No133 (70.4)58 (29.6)1.63 (1.02–2.59)0.0401.49 (0.86–2.57)0.158
Do you use personal protective equipment (PPE)?
Yes112 (59.9)75 (40.1)ref ref
No97 (72.4)37 (27.6)1.76 (1.08–2.83)0.0211.55 (0.87–2.74)0.134
Is the use of PPE appropriate for your job task?
Yes83 (60)55 (40)ref
No126 (69)57 (31)1.46 (0.92–2.33)0.106
Is the personal protective equipment easy
accessible?
Yes96 (62.7)57 (37.3)ref -
No113 (67.3)55 (32.7)1.22 (0.77–1.93)0.397-
Are there on-the-job trainings?
Yes132 (65.3)70 (34.7)ref -
No77 (64.7)42 (35.3)0.97 (0.61–1.56)0.907-
Did your employer provide you with comprehensive training on health and safety issues?
Yes117 (67.2)57 (32.8)ref -
No92 (62.7)55 (37.3)0.82 (0.51–1.29)0.383-
Do you have effective incident reporting procedures that is known for all
employees?
Yes161 (63.6)92 (36.4)ref -
No48 (70.6)20 (29.4)1.37 (0.77–2.45)0.287-
Are all accidents investigated in a timely manner to improve safety in the workplace?
Yes162 (64.5)89 (35.5)ref -
No47 (67.1)23 (32.9)1.12 (0.64–1.97)0.686-
Are pre-employment physical examinations offered by your employer?
Yes53 (71.6)21 (28.4)ref
No156 (63.2)91 (36.8)0.7 (0.39–1.19)0.182
Does your employer provide periodic health examinations?
Yes13 (76.5)4 (23.5)ref -
No196 (64.5)108 (35.5)0.56 (0.18–1.76)0.319-
Sociodemographic variables
Age group
18–30117 (65.4)62 (34.6)refref
31–4469 (64.4)38 (35.6)0.96 (0.58–1.59)0.880
≥4523 (65.7)12 (34.3)1.02 (0.47–2.18)0.968
Education
Never being in school12 (63.2)7 (36.8)0.94 (0.35–2.52)0.908
Primary school86 (64.7)45 (35.3)1.08 (0.67–1.74)0.762
Secondary school and above111 (65.7)60 (34.3)refref
Working years
≤4 years169 (69)76 (31)0.50 (0.30–0.85)0.0101.98 (1.05–3.73)0.035
>4 years40 (52,3)36 (47.7)ref ref
Organizational variables
Section
Furnace81 (58.3)58 (41.7)refrefrefref
Rolling mill128 (70.3)54 (29.7)1.56 (0.07–2.70)0.0251.56 (0.93–2.65)0.095
Working hours per day
≤10 h38 (49.4)39 (50.6)refrefref
>10 h171 (70.1)73 (29.9)2.40 (1.42–4.06)0.0012.71 (1.52–4.83) 0.001
Shift work
Yes129 (70.1)55 (29.9)0.60 (0.38–0.95)0.0301.87 (1.06–3.27) 0.030
No80 (58.4)57 (41.6)ref
OR = Odds ratio; AOR = adjusted odds ratio, adjusted for age group, education level, section, working hours, and shift work; 95% CI = 95% confidence interval.
Table 3. Occupational injury severity and occupational health safety practices among workers in the production line (n = 321).
Safety Practice VariableSeverity of Occupational
Injury—No (%)
OR (95%CI)p-ValueAOR (95%CI)p-Value
1–3 Days Lost>3 Days Lost
Does your workplace have a written occupational health and safety policy?
Yes47 (64.4)26 (35.6)refrefrefref
No88 (64.7)48 (35.3)0.99 (0.54–1.79)0.9630.61 (0.26–1.33)0.211
Do safety officers and safety supervisors carry out safety inspections at regular intervals to detect hazards?
Yes48 (63.2)28 (36.8)refrefrefref
No87 (65.4)46 (34.6)0.90 (0.50–1.63)0.7430.68 (0.32–1.41)0.298
Do you use PPE?
Yes68 (60.7)44 (39.3)refrefref
No67 (69)30 (31)0.69 (0.39–1.23)0.2080.86 (0.44–1.70)0.673
Is the use of PPE appropriate for your job task?
Yes47 (56.6)36 (43.4)refrefref
No88 (69.8)38 (30.2)0.56 (0.32–1.00)0.0520.36 (0.15–0.85)0.019
Is personal protective equipment easy
accessible?
Yes62 (64.6)34 (35.4)refrefrefref
No73 (64.6)40 (35.4)0.99 (0.57–1.77)0.9982.26 (0.85–6.04)0.104
Are there on-the-job trainings?
Yes86 (65.2)46 (34.8)refrefrefref
No49 (63.6)28 (36.4)1.07 (0.59–1.92)0.8250.98 (0.42–2.30)0.966
Did your employer provide you with comprehensive training on health and safety issues?
Yes79 (67.5)38 (32.5)refrefrefref
No56 (60.9)36 (39.1)1.34 (0.76–2.36)0.3190.83 (0.33–2.10)0.694
Do you have an effective incident
reporting procedure that is known by
all employees?
Yes100 (62.1)61 (37.9)refrefrefref
No35 (72.9)13 (27.1)0.61 (0.30–1.24)0.1720.85 (0.18–4.02)0.836
Are all accidents investigated in a timely manner to improve safety in the workplace?
Yes101 (62.3)61 (37.7)refrefrefref
No34 (72.3)13 (27.7)0.63 (0.31–1.29)0.2090.51 (0.11–2.25)0.372
Are pre-employment physical examinations offered by the employer?
Yes37 (69.8)16 (30.2)ref
No98 (62.8)58 (37.2)1.37 (0.70–2.68)0.3590.83 (0.63–5.35)0.268
Does your employer provide periodic health examinations?
Yes7 (53.8)6 (46.2)refrefrefref
No128 (65.3)68 (34.7)0.62 (0.20–1.92)0.4060.41 (0.09–1.82)0.241
OR = Odds ratio, AOR = adjusted odds ratio, adjusted for age group, education level, section, working hours, and shift 95% CI = 95% confidence interval.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.