


Abstract
Cancer now ranks among the leading causes of death in Kenya, with approximately 35,867 new cases and 22,888 deaths annually, and outcomes remain constrained less by the availability of therapy than by the diagnostic pathway that must precede it. A national pathology workforce numbering in the low hundreds serves a population exceeding fifty million, and delayed or absent tissue diagnosis drives late presentation across the five malignancies that account for most of the national burden. Artificial intelligence offers a mechanism to extend interpretive capacity in a system where human expertise cannot be scaled at the rate the disease burden demands. This communication sets out a prioritized research agenda spanning smartphone-assisted visual inspection of the cervix, breast ultrasound classification and histopathological grading, morphological and immunophenotypic triage of hematolymphoid neoplasms, radiomic triage of thoracic and hepatic disease, and AI-assisted radiotherapy contouring. We present a six-stage methodological pipeline covering stakeholder engagement, local dataset curation, transfer learning, validation, usability assessment, and data governance, together with a tiered adoption framework matched to laboratory capability and the workforce competencies required for safe clinical supervision of these systems. The agenda is directed at early-career investigators and is transferable to comparable low- and middle-income settings.
1. Introduction
In 2024, the global cancer burden was estimated at approximately 20.6 million new cancer cases and 9.8 million cancer-related deaths worldwide [1]. According to the World Health Organization (WHO), cancer remains a major contributor to premature mortality, with more than 4.8 million cancer deaths occurring among adults aged 30–69 years, as reported in the Global Status Report on Cancer 2026 [2]. Globally, approximately one in five people develops cancer during their lifetime, while one in nine men and one in thirteen women dies from the disease before the age of 75 years. The WHO projects that annual cancer cases could reach 35 million by 2050, representing an increase of approximately 77% from 2022 estimates [3]. Despite progress in cancer prevention, screening, and early detection, substantial inequalities in treatment outcomes persist across countries. For example, breast cancer survival is considerably higher in high-income countries than in low-income countries, reflecting differences in access to timely diagnosis and effective treatment. Furthermore, fewer than one-third of countries include cancer care services within their universal health coverage benefit packages [3]. These trends underscore the urgent need to strengthen cancer prevention, screening, diagnostic services, treatment, and supportive care, particularly in resource-constrained settings [4].
In sub-Saharan Africa (SSA), cancer represents an increasing public health challenge. Estimates for 2022 indicate that the region experienced approximately 1,154,584 new cancer cases and 754,574 cancer-related deaths, with a substantial proportion of cases concentrated in a limited number of countries [5]. Despite bearing a considerable share of the global cancer burden, SSA has access to only a small proportion of the world’s healthcare workforce, creating substantial constraints on cancer prevention, diagnosis, treatment, and follow-up [6,7]. Evidence also indicates that the burden of several cancers has increased across the region over recent decades [8]. Strengthening cancer surveillance, improving the quality and coverage of cancer registry data, and systematically monitoring national cancer control strategies are therefore essential to improving cancer outcomes in SSA [9].
In Kenya, as in many low- and middle-income countries (LMICs) in SSA, cancer constitutes a major public health challenge, contributing substantially to morbidity, mortality, and healthcare expenditure [7,10]. National vital statistics and analyses of cancer service provision indicate that cancer is an important cause of mortality and that access to timely, effective cancer care remains uneven [11,12]. The situation is exacerbated by limited screening capacity, delayed diagnosis, inadequate treatment availability, and gaps in supportive care [13,14]. Socioeconomic inequalities, low public awareness, inadequate health financing, and disparities in access to healthcare between urban and rural populations further constrain the delivery of equitable cancer services in Kenya [15].
Recent estimates reported by the National Cancer Institute Kenya indicate that the country records approximately 35,867 new cancer cases and 22,888 cancer-related deaths annually, with 76,165 people living with cancer within five years of diagnosis [16]. Breast cancer is the most frequently diagnosed cancer, accounting for 5822 new cases (16.2%), followed by cervical cancer with 4294 cases (12.0%), prostate cancer with 3601 cases (10.0%), oesophageal cancer with 2532 cases (7.1%), and colorectal cancer with 2525 cases (7.0%). Collectively, these five cancer types account for more than half of all reported cancer diagnoses in Kenya and represent important priorities for prevention, early detection, screening, diagnosis, and treatment [16].
Accurate pathological diagnosis is fundamental to oncology because treatment decisions depend on establishing the tumour type, grade, and, where appropriate, molecular characteristics. However, limited diagnostic capacity remains a major constraint on cancer control in Kenya and other resource-constrained settings. The Lancet Commission on Diagnostics highlighted the substantial global gap in access to diagnostic services, particularly in low-resource health systems [17]. Pathology services in many African countries face severe shortages of trained personnel, limited infrastructure, and unequal geographical distribution of expertise [18,19]. Although published estimates of Kenya’s pathology workforce vary according to the definitions and professional categories included, available evidence indicates that specialist capacity remains limited and concentrated in major urban centres and teaching hospitals [20]. Consequently, prolonged turnaround times for biopsy and cytology results can delay treatment initiation and potentially allow disease progression before appropriate clinical management begins.
Artificial intelligence (AI) offers opportunities to strengthen cancer care by supporting clinical decision-making, improving the interpretation of diagnostic images, and extending the capabilities of overstretched healthcare professionals. These applications may be particularly valuable in health systems where shortages of specialist personnel and diagnostic infrastructure constrain access to timely care [21]. However, AI should be implemented as a tool to augment, rather than replace, healthcare professionals. Its effectiveness will depend on clinical validation, integration into existing workflows, appropriate infrastructure, and equitable access to the resulting services.
Against this background, AI applications should be prioritized according to their potential to address specific bottlenecks across the cancer care pathway. Particular attention should be given to settings where shortages in diagnostic expertise, infrastructure, and specialist personnel contribute to delayed care. The following sections examine priority opportunities for AI across cancer screening, diagnostic imaging, digital pathology, and treatment planning, emphasizing interventions that are clinically relevant, technically feasible, and adaptable to resource-constrained settings.
2. Priority AI Interventions in Kenya
The AI applications discussed in this section were selected according to their relevance to Kenya’s cancer burden, the clinical bottlenecks they could address, and their potential feasibility within resource-constrained healthcare systems. Prioritisation considers five dimensions: (i) disease burden and unmet clinical need; (ii) availability and quality of data and supporting infrastructure; (iii) expected clinical and operational benefits; (iv) validation, safety, and human oversight requirements; and (v) implementation costs, workforce capacity, and institutional readiness. Particular attention is given to applications that could support early detection, reduce diagnostic delays, or extend the capacity of existing healthcare professionals. However, clinical need alone does not establish implementation feasibility, and the availability of representative local data, appropriate reference standards, and sustainable infrastructure must also inform decisions about adoption. Table 1 summarises these considerations for the principal AI applications discussed below.
Table 1.
Summary of priority AI interventions for cancer care in Kenya.
Table 1 provides a qualitative prioritisation framework rather than a formal economic evaluation or a verified assessment of national deployment readiness. Applications supported by existing clinical workflows and accessible retrospective data may be suitable for initial proof-of-concept studies, whereas applications requiring specialised infrastructure, confirmatory laboratory testing, or substantial workflow changes may require additional investment before evaluation. Across all applications, progression towards clinical implementation should depend on independent validation, acceptable safety and fairness, meaningful clinician oversight, data governance, and evidence of feasibility in the intended healthcare setting. The relative priorities should be revised as local validation results, implementation costs, and institutional capacity become clearer.
2.1. Cervical Cancer Screening
Cervical cancer remains a major cause of cancer-related mortality among women in Kenya, despite being largely preventable through early detection and treatment of precancerous lesions [22]. Kenya’s cervical cancer screening programmes primarily rely on Visual Inspection with Acetic Acid (VIA), cervical cytology (Pap smear), and human papillomavirus (HPV) DNA testing [23]. However, the implementation of these screening approaches remains challenging within resource-constrained healthcare systems, particularly because of limitations in screening capacity, diagnostic services, and access to treatment [24,25].
VIA is inexpensive and relatively easy to implement in low-resource settings, but its diagnostic performance can depend on the experience of the healthcare provider, potentially resulting in inter-observer variability. Comparative evaluations of VIA, cervical cytology, and histopathology highlight the importance of diagnostic accuracy when identifying precancerous and malignant cervical lesions [26]. Pap smear cytology requires trained laboratory personnel and pathology services, which remain limited in many resource-constrained settings [18,19]. These limitations may contribute to diagnostic delays and constrain screening coverage. Although HPV DNA testing offers an important approach to cervical cancer screening, its implementation also depends on the availability, affordability, and operational feasibility of appropriate testing platforms [27].
Artificial intelligence (AI) offers an opportunity to standardise image interpretation and potentially expand diagnostic capacity. Deep learning methods, particularly convolutional neural networks (CNNs), have demonstrated potential for analysing colposcopic and cytological images to support the early detection of cervical cancer [28]. When integrated with smartphone-based cervical imaging, AI systems could provide decision support at the point of care, potentially reducing diagnostic subjectivity and supporting healthcare workers in primary healthcare facilities where specialist expertise is limited. Emerging reports on AI-assisted cervical cancer screening in rural Kenya also highlight the potential relevance of these technologies to underserved populations [29].
Within Kenya, an AI-enabled cervical screening platform could integrate smartphone-based cervical imaging with deep-learning algorithms deployed through cloud-based infrastructure or, preferably in bandwidth-constrained areas, edge computing. Algorithms trained on appropriately annotated cervical images could assist in classifying images as normal or suspicious for low-grade or high-grade cervical lesions. The system could also flag cases requiring referral for expert colposcopy, further diagnostic assessment, or treatment. Such classifications would need to be validated against accepted clinical and histopathological reference standards before clinical implementation.
A feasible proof-of-concept study could involve community health workers performing VIA and acquiring cervical images using smartphone-based imaging devices across selected county health facilities. AI-generated classifications would be evaluated against expert colposcopist assessments and, where clinically indicated and ethically appropriate, histopathological findings. A human-in-the-loop approach would allow trained clinicians to review AI outputs, resolve uncertain cases, and retain responsibility for clinical decisions.
The primary outcome measures would include sensitivity, specificity, and the area under the receiver operating characteristic curve (AUC). Additional outcomes could include inter-rater agreement between AI predictions and expert assessments, referral accuracy, image acquisition failure rates, and time to clinical decision. The study should also evaluate technical feasibility, performance across participating sites, and the potential effects of connectivity limitations on system reliability. These findings would help establish whether AI-assisted smartphone screening could provide a safe, scalable, and contextually appropriate adjunct to cervical cancer prevention services in Kenya.
2.2. Breast Cancer Diagnosis
Breast cancer is one of the most frequently diagnosed cancers among women in Kenya and remains a leading cause of cancer-related mortality, partly because many patients present with advanced disease [30]. Breast ultrasound is an important imaging modality for breast cancer assessment, particularly in low- and middle-income countries, although its diagnostic performance may depend on operator expertise and image acquisition quality [31]. Delays in pathology reporting and shortages of specialist pathologists further constrain timely cancer diagnosis in resource-limited settings [18,19].
Artificial intelligence (AI) has demonstrated considerable potential to improve radiological and pathological diagnosis. Convolutional neural networks trained on publicly available datasets, including the Breast Ultrasound Images Dataset (BUSI), have been investigated for differentiating benign from malignant breast lesions [32,33,34]. Fine-tuning these models using locally acquired Kenyan ultrasound images could improve their generalisability across patient populations, healthcare settings, and imaging equipment. Explainable AI techniques, including Gradient-weighted Class Activation Mapping (Grad-CAM), can also highlight image regions that contribute to model predictions, potentially improving interpretability and supporting clinical review [35].
Digital pathology provides another important opportunity to strengthen breast cancer diagnosis. Whole-slide imaging (WSI) enables histopathological slides to be digitised for computational analysis. Deep-learning algorithms have demonstrated potential for automated tumour detection, mitotic counting, nuclear pleomorphism assessment, and histological grading, with possible benefits for diagnostic consistency and pathology workflow efficiency [36,37]. In addition, AI-assisted whole-slide image analysis may support more objective and reproducible assessment of breast cancer biomarkers, including oestrogen receptor (ER), human epidermal growth factor receptor 2 (HER2), and Ki-67. Such methods could be particularly valuable when evaluating equivocal HER2 immunohistochemistry results, including 2+ cases requiring additional testing, and when characterising HER2-low disease [38,39]. However, these applications require appropriate analytical and clinical validation before routine implementation. Overall, AI is best positioned as a clinical decision-support tool that complements pathologist expertise, potentially reduces interobserver variability, and improves diagnostic efficiency [38].
A retrospective proof-of-concept study could evaluate diagnostic concordance between AI-generated pathology assessments and diagnoses made by consultant pathologists using archived breast biopsy specimens from Kenyan referral hospitals. Agreement could be assessed using sensitivity, specificity, Cohen’s coefficient, histological grading concordance, and changes in pathology reporting turnaround time. Such an evaluation would provide preliminary evidence on the feasibility and clinical utility of AI-assisted breast cancer diagnosis in the Kenyan healthcare context.
2.3. Hematolymphoid Malignancies and the Morphological Gap
Solid tumours dominate national cancer control planning, yet haematological and lymphoid neoplasms carry a distinct diagnostic burden that no imaging algorithm will address. Burkitt lymphoma remains endemic across the malaria belt of East Africa, presents overwhelmingly in children, and is curable at rates that depend more on the interval between presentation and treatment than on any other single variable. Diffuse large B-cell lymphoma, Hodgkin lymphoma, and HIV-associated lymphoproliferative disease together account for a substantial share of the oncological workload at national referral hospitals, while acute leukaemias in children arrive with a clock already running. Accurate subclassification of these diseases depends on immunophenotyping by flow cytometry or immunohistochemistry and, increasingly, on cytogenetic and molecular studies, all of which are concentrated in a small number of Kenyan laboratories and are frequently unavailable at the point of first clinical contact [40,41].
Three applications are tractable with existing technology. Automated morphological screening of peripheral blood and bone marrow aspirate smears, whether through dedicated digital cell morphology systems or through microscope-mounted smartphone capture, can triage films containing blasts, dysplastic changes, or abnormal lymphoid populations to a pathologist, converting the scarce resource of expert interpretation into a review function rather than a primary screening function [42]. Deep-learning classification of haematoxylin and eosin sections from lymph node and extranodal biopsies can generate a prioritized differential and, in published work, predict immunophenotypic and molecular features that would otherwise consume an antibody panel the laboratory cannot afford to run on every case. Machine-learning interpretation of flow cytometry list-mode data can flag abnormal populations and standardize gating, a task in which inter-operator variability is well documented and in which local subspecialty expertise is thinnest [43].
A proof-of-concept study in this domain would be inexpensive relative to the imaging work described above, because the input material already exists in the archive. Stored Giemsa-stained films and archival lymph node blocks from national and academic referral hospitals could be digitized and used to train and validate a blast-detection and lymphoma-triage model against the consensus diagnosis of a haematopathology review panel [44]. Outcome measures of interest would include sensitivity for blasts, negative predictive value for the exclusion of acute leukaemia, concordance with WHO classification categories, and the reduction in immunohistochemical stains required per case. Negative predictive value deserves particular emphasis, because where the realistic alternative to an algorithm is no expert morphological review at all, the clinically decisive property of the tool is its capacity to safely release normal material rather than its accuracy on rare and difficult cases [45].
2.4. The Pre-Analytic Constraint on Computational Pathology
Every computational pathology proposal in this roadmap rests on an assumption that deserves to be stated rather than presumed: a technically adequate slide exists. Whole-slide imaging digitizes only what the laboratory produced, and a model trained on well-fixed, evenly sectioned, consistently stained material from a high-resource reference laboratory will degrade against slides made under conditions of interrupted formalin supply, prolonged cold ischaemia, manual processing, variable microtome performance, and haematoxylin batches that drift across a working week. Stain variation alone has been shown to shift the output of deep-learning classifiers [46]. Stain normalization, colour augmentation, and domain adaptation should therefore be written into the model development protocol rather than discovered during external validation.
Pathology in this context should be understood as a diagnostic system rather than histopathology alone. Cancer diagnosis depends on an interconnected pathology and laboratory medicine infrastructure spanning specimen acquisition and processing, histology and cytology, haematology and flow cytometry, immunohistochemistry, molecular diagnostics, and the laboratory information systems and quality processes that connect these activities. Artificial intelligence may improve individual steps within this system, but its clinical value ultimately depends on whether an adequate specimen can be obtained, processed, characterized, integrated with complementary laboratory findings, and reported in time to guide treatment. Investment in computational pathology should therefore strengthen the diagnostic pathway around the algorithm, including laboratory workforce, quality management, specimen logistics, interoperability, and access to ancillary testing.
This is not an argument against digital pathology in Kenya. Rather, the first investment in any national AI pathology programme should be at the histology bench, and algorithm development should be paired with standardization of fixation and staining together with participation in external quality assessment schemes. Scanner access deserves equal candour, since whole-slide scanners remain concentrated in a small number of institutions and the realistic near-term substitute is microscope-mounted digital capture of selected fields. This constrains model architecture and should be reflected in study design from the outset [47]. The diagnostic pathway begins with a clinician who decides to biopsy, continues through a specimen that reaches a laboratory intact and correctly labelled, and ends with a report that reaches the treating team in time to change management. Artificial intelligence can compress the interpretive segment of that pathway; it cannot manufacture the segments preceding it.
2.5. Cancer Imaging and Radiomics
Medical imaging underpins cancer diagnosis, staging, treatment planning, and surveillance. However, Kenya continues to experience a shortage of subspecialised oncological radiologists, particularly outside tertiary referral centres [48]. Consequently, subtle lesions may be overlooked, reporting delays may occur, and advanced quantitative imaging biomarkers remain underutilised.
Artificial intelligence (AI) offers opportunities to augment radiological interpretation while facilitating the integration of radiomics into routine oncology practice. Radiomics involves extracting quantitative imaging features that describe tumour morphology, texture, and heterogeneity, including characteristics that may not be readily discernible through visual assessment alone [49]. When combined with machine learning algorithms, these features may support tumour characterisation, treatment-response prediction, and prognostic assessment.
Transfer learning using pretrained imaging models may facilitate the automated detection and characterisation of lesions. For example, pretrained neural networks have been investigated for focal liver lesion diagnosis using ultrasound imaging [50]. In addition, nnU-Net-based approaches have been evaluated for automated tumour segmentation and tumour-volume estimation in medical imaging [51]. Automated segmentation can enable more reproducible tumour-volume measurements and facilitate longitudinal treatment monitoring.
A Kenyan proof-of-concept study could utilise de-identified abdominal computed tomography (CT) scans from Kenyatta National Hospital to evaluate AI-based liver lesion segmentation. Performance could be assessed using the Dice Similarity Coefficient (DSC), Hausdorff Distance, and volumetric agreement against expert manual annotations. Extracted radiomic signatures could subsequently be investigated for associations with treatment response, recurrence, and overall survival.
2.6. Radiotherapy Planning and Digital Pathology
Radiotherapy planning requires precise delineation of tumours and surrounding organs at risk (OARs). In Kenya, workforce constraints and limitations in oncology service capacity may contribute to delays in cancer care and treatment planning [52]. Deep-learning segmentation architectures have been investigated for automated organ-at-risk contouring and radiotherapy planning. Recent reviews describe their potential to improve contouring efficiency while highlighting the importance of evaluating segmentation accuracy, interobserver variability, and dosimetric consequences [53,54]. Such systems may improve workflow efficiency in cervical brachytherapy and external-beam radiotherapy, provided that their performance is validated for the relevant anatomical sites and clinical settings. AI also offers opportunities in computational pathology. Molecular biomarkers, including human epidermal growth factor receptor 2 (HER2), Ki-67, and microsatellite instability (MSI), can inform cancer classification and treatment selection. However, their assessment may require specialised laboratory methods, including immunohistochemistry (IHC), polymerase chain reaction (PCR), or sequencing, depending on the biomarker and clinical indication. Access, affordability, and laboratory capacity remain important considerations when implementing precision oncology in resource-constrained settings [39,55]. Recent advances in computational pathology have also investigated the prediction of clinically relevant molecular and morphological characteristics directly from routine haematoxylin-and-eosin (H&E)-stained whole-slide images. Weakly supervised learning is particularly relevant because it can utilise slide-level labels without requiring exhaustive pixel-level annotations for every tissue region [56]. A proof-of-concept implementation in Kenya could compare conventional manual cervical brachytherapy planning with AI-assisted workflows to quantify changes in contouring time and evaluate contour quality using the Dice Similarity Coefficient, Hausdorff Distance, and clinician acceptability scores. In parallel, AI models for predicting MSI status from archived digital pathology slides could be evaluated against validated molecular reference tests. Evaluation outcomes could include diagnostic accuracy, calibration, cost-effectiveness, and workflow efficiency. Such studies should incorporate appropriate data governance, external validation, and clinician oversight before clinical deployment.
3. Methodological Roadmap
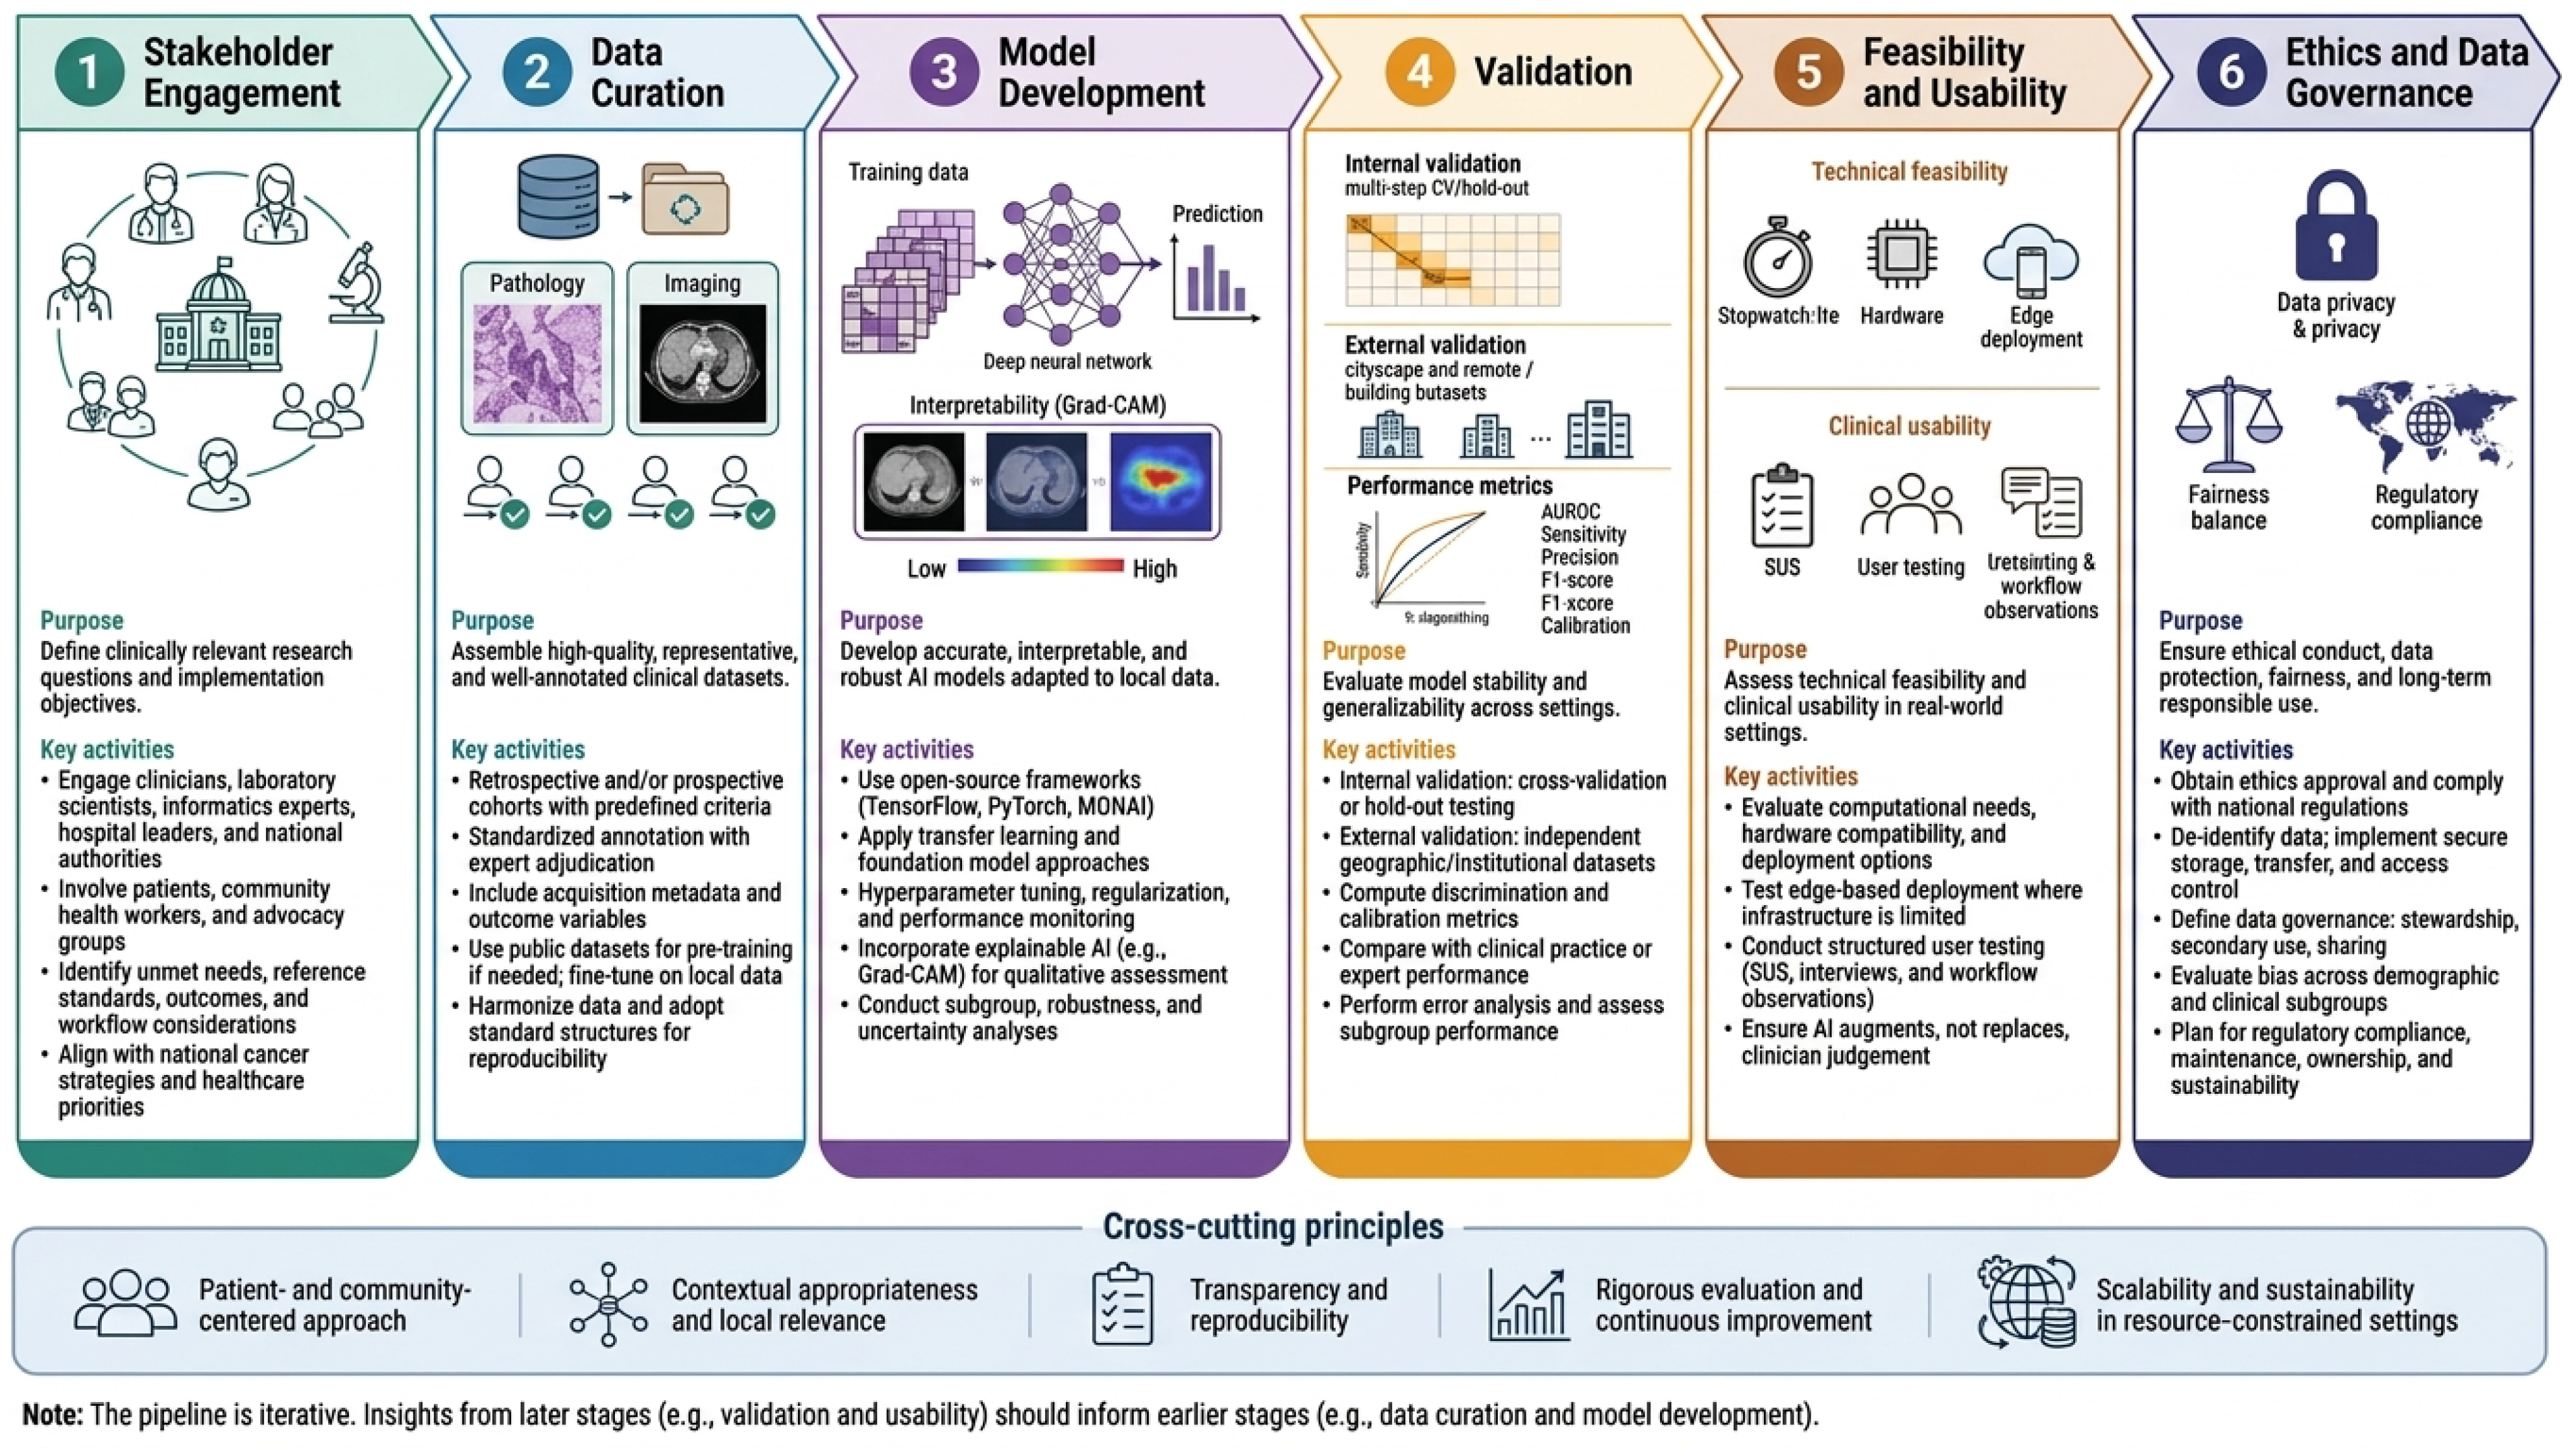
We present a six-stage methodological pipeline for conducting proof-of-concept artificial intelligence (AI) studies in cancer research within resource-constrained healthcare systems (see Figure 1). The pipeline provides a structured framework that integrates clinical problem definition, data generation, model development, validation, implementation assessment, and governance considerations.
Figure 1.
Proof of concept workflow.
Unlike conventional AI development workflows that prioritize predictive performance, this framework emphasizes clinical relevance, representative datasets, implementation readiness, and responsible AI governance. Although developed using Kenya as an exemplar LMIC setting, the pipeline is designed to be transferable to comparable healthcare environments and to support early-career researchers undertaking clinically oriented AI research. To facilitate practical implementation, each stage should be associated with defined activities, tangible deliverables, and explicit go/no-go criteria. These criteria provide decision points for determining whether a project is sufficiently feasible, methodologically sound, and clinically relevant to proceed to the next stage. The proposed criteria are intended as adaptable guidance rather than universal thresholds, as their application will depend on the research question, available resources, clinical risks, and intended use of the AI system. Table 2 summarises the activities, expected deliverables, and recommended progression criteria for the six stages.
Table 2.
Actionable six-stage methodological roadmap for proof-of-concept AI research in cancer in resource-constrained healthcare systems.
Progression through the roadmap should be iterative rather than strictly linear. Failure to meet a criterion should trigger documented reassessment, data improvement, model revision, or reconsideration of the intended use. Importantly, successful completion of a proof-of-concept study does not establish clinical utility or justify routine clinical deployment. Such claims require appropriately designed prospective evaluation and evidence that the system is safe, effective, equitable, and feasible within the intended healthcare setting.
3.1. Stakeholder Engagement
The pipeline begins with stakeholder engagement to define clinically relevant research questions and implementation objectives before model development. Clinical stakeholders, including oncologists, pathologists, radiologists, surgeons, laboratory scientists, and clinical informatics specialists, identify priority clinical problems, establish reference standards, define outcome measures, and evaluate integration within existing diagnostic and treatment workflows. Engagement with hospital administrators and national health authorities aligns research activities with institutional priorities and national cancer control strategies. Patient representatives, community health workers, and cancer advocacy organisations are incorporated throughout the planning phase to identify barriers to implementation, improve acceptability, and ensure that proposed AI solutions address locally relevant healthcare needs. Early stakeholder engagement therefore informs study design, data acquisition, annotation protocols, evaluation criteria, and implementation planning. Stakeholders should also define acceptable performance thresholds, clinically significant errors, and implementation requirements before evaluation begins. Evidence of effectiveness from other settings can inform study design but cannot replace local assessment of clinical relevance, acceptability, and workflow compatibility in Kenya.
3.2. Data Curation
Clinical datasets are assembled from retrospective and/or prospective cohorts using predefined inclusion and exclusion criteria. Dataset development prioritizes clinical representativeness, annotation quality, and demographic diversity rather than dataset size alone. Proof-of-concept studies typically include several hundred participants, although sample size requirements depend on disease prevalence, imaging modality, and the intended clinical application. Annotations are generated using standardized protocols developed collaboratively with domain experts. Pathology datasets include tumour classification, grading, and segmentation according to established diagnostic criteria, whereas imaging datasets include acquisition metadata together with clinically relevant outcome variables. Annotation discrepancies are documented and resolved through expert adjudication to preserve annotation consistency while acknowledging clinically meaningful uncertainty. Where sufficiently large local datasets are unavailable, publicly available datasets may be used for pre-training before transfer learning and fine-tuning using locally acquired data. Because disease epidemiology, imaging protocols, healthcare delivery, and population characteristics differ across settings, externally derived datasets are not considered substitutes for representative local cohorts. Data harmonization procedures and standardized data structures are incorporated to improve reproducibility and facilitate future multicentre collaborations. Retrospective Kenyan datasets should be used to assess data quality, representativeness, and potential sources of bias. Where local data are limited, external datasets may support initial model development; however, their use does not establish validity in Kenyan populations. Data-sharing arrangements should also comply with applicable ethical, privacy, and institutional governance requirements.
3.3. Model Development
Models are developed using open-source deep learning frameworks (TensorFlow, PyTorch, or MONAI) to maximize reproducibility, transparency, and accessibility. Transfer learning and foundation-model approaches are preferentially adopted to reduce annotation requirements while enabling adaptation to local clinical datasets. Model optimization includes hyperparameter tuning, regularization, and iterative performance monitoring using predefined validation datasets. Explainable AI techniques, including Gradient-weighted Class Activation Mapping (Grad-CAM), are incorporated to enable qualitative assessment of prediction localization by clinical experts. These visualization methods support interpretation of model outputs but are not regarded as definitive evidence of model reasoning. Model development further includes robustness testing, uncertainty estimation, and subgroup analyses to evaluate performance across demographic, clinical, and disease-specific subpopulations and to identify potential sources of algorithmic bias before external evaluation. Although transfer learning and explainability methods are established research approaches, their effectiveness and reliability in specific Kenyan clinical settings remain empirical questions. Models should therefore be compared with appropriate baselines, assessed for data leakage, and tested for subgroup disparities and robustness before clinical evaluation.
3.4. Validation
Model evaluation follows a sequential validation strategy comprising both internal and external assessment. Internal validation employs cross-validation or independent hold-out datasets to assess model stability during development. External validation uses geographically or institutionally independent datasets to evaluate generalizability across healthcare settings. Performance is quantified using standard discrimination metrics, including the area under the receiver operating characteristic curve (AUROC), sensitivity, specificity, precision, recall, and F1-score, together with calibration analyses where appropriate. Whenever suitable reference standards exist, AI performance is compared with expert interpretation or current clinical practice. Comprehensive error analysis is performed to identify clinically significant failure modes, characterize model uncertainty, and evaluate performance variability across patient subgroups. A common translation pathway should guide all applications: (i) retrospective validation using representative Kenyan data; (ii) prospective evaluation in intended clinical workflows; (iii) implementation assessment of usability, safety, costs, and clinical utility; and (iv) post-deployment monitoring for model drift, performance disparities, and emerging risks. Progression between stages should require predefined acceptance criteria and appropriate clinical oversight. Internationally reported performance and retrospective proof-of-concept results should not, on their own, be interpreted as evidence of readiness for routine clinical use in Kenya.
3.5. Clinical Feasibility and Usability Assessment
Implementation feasibility is assessed by evaluating computational requirements, inference time, hardware compatibility, and deployment within representative clinical environments. In settings with constrained computational infrastructure, edge-based deployment strategies are considered to minimize dependence on cloud computing and uninterrupted internet connectivity. Teams should incorporate implementation science principles to rigorously evaluate the feasibility and usability of the AI intervention/tool. Operational feasibility also considers power reliability, hardware availability, connectivity, data storage, system maintenance, and technical support. Economic assessment considers total implementation and lifecycle costs, including equipment, software, maintenance, workforce training, and model updates, alongside potential clinical and operational benefits. AI-based approaches should be compared with realistic alternatives, including conventional pathologist-led diagnosis, telepathology, and investments in existing diagnostic services, to establish their relative cost-effectiveness and suitability for local settings. Clinical usability is evaluated through structured user testing involving intended end-users. Standardized usability instruments, including the User Experience Questionnaire (UEQ), are combined with qualitative interviews and workflow observations to assess usability, interpretability, workflow integration, and user acceptance. Throughout the evaluation process, AI systems are considered clinical decision-support tools intended to augment, rather than replace, clinician decision-making. Workforce readiness is assessed through staff availability, training requirements, and the capacity to interpret AI outputs and manage system failures. Long-term sustainability requires clear maintenance responsibilities, ongoing technical support, and monitoring of model performance. Feasibility findings should account for differences in institutional resources and determine whether AI provides meaningful, affordable, and sustainable benefits compared with existing clinical workflows.
3.6. Ethics and Data Governance
All studies should be conducted following institutional ethics approval and applicable national regulations governing human participant research, data protection, and information security. Clinical datasets are de-identified before analysis, and secure procedures are implemented for data storage, transfer, and controlled access. Data governance frameworks define responsibilities for data stewardship, secondary data use, institutional ownership, and collaborative data sharing. Bias assessment is integrated throughout model development by evaluating performance across demographic and clinical subgroups. Fairness analyses identify systematic performance disparities that could contribute to inequitable healthcare delivery and inform subsequent model refinement. Long-term considerations, including regulatory compliance, post-deployment monitoring, model maintenance, sustainability, and institutional capacity building, are incorporated during study planning to facilitate responsible clinical translation and sustainable implementation of AI technologies within LMIC healthcare systems. However, AI models may experience domain shift and reduced generalisability across institutions due to differences in patient populations, staining protocols, scanners, and clinical workflows. External validation across diverse healthcare settings, subgroup-based bias assessment, and continuous post-deployment monitoring are therefore essential to identify performance disparities and model drift. Predefined intervention thresholds and qualified human oversight should guide model updates and clinical decisions, ensuring that AI complements rather than replaces the judgement of pathologists. Digital pathology raises a governance question that is different from radiological imaging. A whole-slide image is a permanent, high-resolution, and effectively inexhaustible representation of a patient’s tissue, and once it leaves the institution that produced it, it can be used to train commercial models indefinitely without further reference to the patient, the reporting pathologist, or the hospital. African datasets have historically been exported under collaborative arrangements that returned publications rather than durable capacity, and a Kenyan artificial intelligence cancer programme should therefore set its terms in advance rather than negotiate them retrospectively. Those terms should specify that primary image repositories remain under Kenyan institutional custody, that model weights derived from Kenyan data are jointly owned, that any commercial application requires a separately negotiated agreement (as proposed by the National Data Governance policy), and that collaborating institutions commit to reciprocal training and infrastructure investment rather than to authorship alone. The Data Protection Act, 2019 and the oversight framework of the National Commission for Science, Technology and Innovation provide the statutory basis, and study protocols should address secondary use explicitly rather than relying on broad consent language that patients cannot meaningfully evaluate. Data sovereignty should extend to secure data storage, controlled access, transparent cross-border transfer arrangements, and safeguards against re-identification and unauthorised secondary use. Governance agreements should explicitly define ownership and control of datasets, model weights, intellectual property, and commercial applications in accordance with applicable legal and ethical requirements. Benefit-sharing arrangements should extend beyond co-authorship to include local infrastructure investment, workforce training, technology transfer, equitable intellectual property arrangements, and affordable access to resulting diagnostic tools. Nevertheless, limited resources, insufficiently representative datasets, and gaps in monitoring capacity may constrain implementation. These limitations should be transparently reported, with sustained local investment and stakeholder participation supporting responsible, equitable, and context-appropriate AI deployment in LMIC healthcare systems.
4. Workforce, Training, and Resource-Stratified Adoption
A roadmap that ends at model validation stops short of the point at which patients benefit. The rate-limiting factor for artificial intelligence in Kenyan cancer care will not be model performance, which is already adequate for several of the tasks described above, but the readiness of the clinical workforce to interpret, supervise, and override these systems. Pathologists, radiologists, oncologists, clinical officers, and community health workers will be asked to act on probabilistic outputs generated by models whose training data they did not select and whose failure modes they have not been taught to recognize. Building that capacity is a curricular problem, and it should be planned alongside the technical work rather than appended to it once deployment has begun. Four competencies define the minimum standard for safe use. Clinical users should be able to state what a given model was trained to do and on which population, recognize the case types that fall outside its training distribution, interpret a probability score or a saliency map as evidence to be weighed against the clinical picture rather than as a verdict to be transcribed, and articulate where diagnostic and medicolegal responsibility resides when the model and the clinician disagree. These competencies map onto the existing architecture of medical education in Kenya, where they can be introduced during undergraduate pathology teaching, consolidated within Master of Medicine training in pathology and radiology, and maintained through continuing professional development delivered by the Kenya Association of Pathologists and the College of Pathologists of East, Central and Southern Africa. Embedding artificial intelligence literacy within postgraduate pathology training carries a second benefit, which is that the trainees who annotate the datasets become the consultants who later supervise the deployed systems, and that continuity is the most reliable safeguard against uncritical adoption. Adoption should be stratified by demonstrated laboratory capability rather than presented as a single national ambition, since deploying a whole-slide imaging workflow into a facility without reliable tissue processing produces a costly failure that sets the wider programme back.
5. Expected Impact and Conclusions
In conclusion, successful translation of AI into routine clinical practice requires methodological approaches that extend beyond algorithm development to encompass clinical validation, implementation science, governance, and healthcare system integration. The six-stage pipeline presented here provides a practical and reproducible framework to guide early-career researchers in developing clinically relevant, transparent, and ethically responsible AI systems for cancer diagnosis within resource-constrained settings. Although related studies demonstrate the potential of AI in cancer diagnosis, their findings cannot be assumed to generalise to Kenya because of differences in patient populations, data quality, equipment, and clinical workflows. Local validation is therefore essential. A common translation pathway should progress from retrospective validation using Kenyan data to prospective clinical evaluation, implementation assessment, and post-deployment monitoring. Progression should depend on predefined performance and safety criteria, ethical and governance requirements, and appropriate human oversight. By aligning computational innovation with clinical priorities, implementation readiness, and responsible data governance, the framework supports the generation of high-quality translational evidence necessary to advance AI from proof-of-concept studies toward sustainable clinical deployment. Wider adoption of similar methodological frameworks may strengthen AI research capacity, promote equitable innovation, and contribute to reducing disparities in access to high-quality cancer diagnostics across sub-Saharan Africa and other LMICs. Ultimately, sustainable AI adoption in Kenya will depend on demonstrated local clinical benefit, affordability, equitable access, and effective integration into existing healthcare services.
Author Contributions
Conceptualization, P.M. and C.N.N.; methodology, A.W.; original draft preparation, P.M. and C.N.N.; review and editing, P.J., N.N., L.W., S.S., K.M.; supervision, A.W. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
During the preparation of this manuscript, the authors used Gemini 3.8 Flash for the purposes of creating the flow diagram.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AI | Artificial Intelligence |
| AUC | Area Under the Curve |
| AUROC | Area Under the Receiver Operating Characteristic Curve |
| BUSI | Breast Ultrasound Images Dataset |
| CNN | Convolutional Neural Network |
| CT | Computed Tomography |
| DNA | Deoxyribonucleic Acid |
| ER | Estrogen Receptor |
| Grad-CAM | Gradient-weighted Class Activation Mapping |
| H&E | Hematoxylin and Eosin |
| HER2 | Human Epidermal Growth Factor Receptor 2 |
| HIV | Human Immunodeficiency Virus |
| HPV | Human Papillomavirus |
| IHC | Immunohistochemistry |
| LMIC | Low- and Middle-Income Country |
| MONAI | Medical Open Network for AI |
| MSI | Microsatellite Instability |
| OAR | Organ at Risk |
| Pap | Papanicolaou (as in Pap smear) |
| PCR | Polymerase Chain Reaction |
| SSA | Sub-Saharan Africa |
| SUS | System Usability Scale |
| VIA | Visual Inspection with Acetic Acid |
| WHO | World Health Organization |
| WSI | Whole-Slide Imaging |
References
- Sung, H.; Filho, A.; Laversanne, M.; Ferlay, J.; Siegel, R.L.; Soerjomataram, I.; Jemal, A.; Bray, F. Global cancer statistics 2024: GLOBOCAN estimates of incidence and mortality worldwide for 34 cancers in 186 countries. CA Cancer J. Clin. 2026, 76, e70090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Global Status Report on Cancer 2026: The Future We Choose Together; WHO: Geneva, Switzerland, 2026; Available online: https://www.who.int/publications/i/item/9789240123977 (accessed on 30 July 2026).
- World Health Organization. Global Cancer Burden Growing, Amidst Mounting Need for Services; WHO: Geneva, Switzerland, 2024; Available online: https://www.who.int/news/item/01-02-2024-global-cancer-burden-growing--amidst-mounting-need-for-services (accessed on 26 July 2026).
- Luo, Q.; Smith, D. Global cancer burden: Progress, projections, and challenges. Lancet 2025, 406, 1536–1537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ugwu, L.; Ajele, W.; Idemudia, E.; Basil, B.; Onyedibe, M.-C.C.; Chidebe, R.C.W.; Nienaber-Rousseau, C.; Ugwoke, U.F.; Khohliwe, C.T. Cancer in Africa, 2022: Incidence, mortality, and age-patterned fatality from GLOBOCAN across 36 cancer types. JCO Glob. Oncol. 2026, 12, e2500663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Atlas, C. Cancer in Sub-Saharan Africa. Available online: https://canceratlas.cancer.org/burden-of-cancer/cancer-in-sub-saharan-africa/ (accessed on 26 July 2026).
- Omotoso, O.; Teibo, J.; Atiba, F.; Oladimeji, T.; Paimo, O.K.; Ataya, F.S.; Batiha, G.E.-S.; Alexiou, A. Addressing cancer care inequities in sub-Saharan Africa: Current challenges and proposed solutions. Int. J. Equity Health 2023, 22, 189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bolarinwa, O.; Bashir, S.; Okyere, J.; Abdi, Y.H.; Salad, H.A.; Dada, O.; Yusuff, A.O. Burden, regional trends and risk factors of breast, cervical, uterine, and ovarian cancers in sub-Saharan Africa, 1990–2023: The Global Burden of Disease 2023. Int. J. Environ. Res. Public Health 2026, 23, 419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bray, F.; Parkin, D.; Network, A.C.R. Cancer in sub-Saharan Africa in 2020: A review of current estimates of the national burden, data gaps, and future needs. Lancet Oncol. 2022, 23, 719–728. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ngwa, W.; Addai, B.W.; Adewole, I.; Ainsworth, V.; Alaro, J.; Alatise, O.I.; Ali, Z.; Anderson, B.O.; Anorlu, R.; Avery, S.; et al. Cancer in sub-Saharan Africa: A Lancet Oncology Commission. Lancet Oncol. 2022, 23, e251–e312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kenya National Bureau of Statistics. Kenya Vital Statistics Report 2024. 2024. Available online: https://www.knbs.or.ke/reports/kenya-vital-statistics-report-2024/ (accessed on 30 July 2026).
- Wambalaba, F.; Wambalaba, A. The inequity of cancer treatment services in Kenya. In The Landscape of Global Health Inequity; Son, B., Ed.; Springer Nature: Cham, Switzerland, 2024; pp. 37–46. [Google Scholar] [CrossRef] [Scilit]
- Nyangasi, M.; McLigeyo, A.; Kariuki, D.; Mithe, S.; Orwa, A.; Mwenda, V. Decentralizing cancer care in sub-Saharan Africa through an integrated regional cancer centre model: The case of Kenya. PLoS Glob. Public Health 2023, 3, e0002402. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kizub, D.; Naik, S.; Abogan, A.; Pain, D.; Sammut, S.; Shulman, L.N.; Martei, Y.M. Access to and affordability of World Health Organization essential medicines for cancer in sub-Saharan Africa: Examples from Kenya, Rwanda, and Uganda. Oncologist 2022, 27, 958–970. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Springer Nature. How Social Determinants of Health and Health System Factors Shape the Breast Cancer Continuum in Kenya; Springer Nature: Berlin, Germany, 2025; Available online: https://link.springer.com/article/10.1007/s12609-025-00596-z (accessed on 28 July 2026).
- National Cancer Institute Kenya. Kenya Records 35,867 New Cancer Cases in Latest GLOBOCAN 2024 Estimates. 10 July 2026. Available online: https://wp.ncikenya.go.ke/2026/07/10/kenya-records-35867-new-cancer-cases-in-latest-globocan-2024-estimates/ (accessed on 28 July 2026).
- Fleming, K.A.; Horton, S.; Wilson, M.L.; Atun, R.; DeStigter, K.; Flanigan, J.; Sayed, S.; Adam, P.; Aguilar, B.; Andronikou, S.; et al. The Lancet Commission on Diagnostics: Transforming Access to Diagnostics. Lancet 2021, 398, 1997–2050. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mudenda, V.; Malyangu, E.; Sayed, S.; Fleming, K. Addressing the shortage of pathologists in Africa: Creation of a MMed programme in pathology in Zambia. Afr. J. Lab. Med. 2020, 9, 974. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilson, M.; Fleming, K.; Kuti, M.; Looi, L.; Lago, N.; Ru, K. Access to pathology and laboratory medicine services: A crucial gap. Lancet 2018, 391, 1927–1938. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- The Lancet. Improving Pathology and Laboratory Medicine in Low-Income and Middle-Income Countries: Roadmap to Solutions. 2018. Available online: https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(18)30459-8/fulltext (accessed on 11 August 2026).
- Hricak, H.; Ward, Z.; Moraes, F.; Scott, A.M.; Dako, F.; Ngwa, W.; Villarreal-Garza, C.; Abdel-Wahab, M.; Avery, S.; Addai, B.W.; et al. Cancer workforce—A global crisis: A Lancet Oncology Commission. Lancet Oncol. 2026, 27, e279–e316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mwenda, V.; Mburu, W.; Bor, J.P.; Nyangasi, M.; Arbyn, M.; Weyers, S.; Tummers, P.; Temmerman, M. Cervical cancer programme, Kenya, 2011–2020: Lessons to guide elimination as a public health problem. ecancermedicalscience 2022, 16, 1442. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Orang’o, E.O.; Were, E.; Rode, O.; Muthoka, K.; Byczkowski, M.; Sartor, H.; Broeck, D.V.; Schmidt, D.; Reuschenbach, M.; Doeberitz, M.; et al. Novel concepts in cervical cancer screening: A comparison of VIA, HPV DNA test and p16INK4a/Ki-67 dual stain cytology in Western Kenya. Infect. Agents Cancer 2020, 15, 57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mwenda, V.; Murage, D.; Kilonzo, C.; Bor, J.-P.; Njiri, P.; Osiro, L.; Nyangasi, M.; Arbyn, M.; Tummers, P.; Temmerman, M. Baseline assessment of cervical cancer screening and treatment capacity in 25 counties in Kenya, 2022. Front. Oncol. 2024, 14, 1371529. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adhiambo, H.F.; Owidi, E.; Okello, P.; Coe, M.; Shin, M.B.; Oluoch, L.M.; Thuo, N.B.; Ihaji, V.; Kerubo, M.B.; Kinyua, A.; et al. Barriers and facilitators to implementing a single-visit, screen-and-treat approach with thermal ablation for cervical cancer prevention in Kenya. PLoS Glob. Public Health 2025, 5, e0005166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- David, J.; Joshi, V.; Jebin Aaron, D.; Baghel, P. A Comparative Analysis of Visual Inspection With Acetic Acid, Cervical Cytology, and Histopathology in the Screening and Early Detection of Premalignant and Malignant Lesions of the Cervix. Cureus 2022, 14, e29762. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siferih, M.; Gedif, G.; Lamesgen, A.; Alamneh, A.A.; Muluneh, A.A.; Melesse, Y.D.; Mihiret, G.T.; Gete, M.; Getnet, A.; Amha, H.; et al. Point-of-care HPV testing for cervical cancer screening in Sub-Saharan Africa: Platform diversity, diagnostic performance, implementation feasibility, and determinants—A scoping review with contextual considerations for Ethiopia. BMC Public Health 2026, 26, 990. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Wang, Q.; Ding, G.; Wang, J.; Tang, Y.; Feng, Y. Artificial intelligence for colposcopic and cytological image analysis in early cervical cancer detection. iScience 2026, 29, 114627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Healthcare in Europe. AI Delivers Cervical Cancer Screening to Rural Areas of Kenya. Available online: https://healthcare-in-europe.com/en/news/ai-delivers-cervical-cancer-screening-to-rural-areas-of-kenya.html (accessed on 28 July 2026).
- Daniels-Donkor, S.S.; Afaya, A. Internet use and uptake of clinical breast examination among Kenyan women of reproductive age. Sci. Rep. 2025, 15, 42574. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iacob, R.; Iacob, E.R.; Stoicescu, E.R.; Ghenciu, D.M.; Cocolea, D.M.; Constantinescu, A.; Ghenciu, L.A.; Manolescu, D.L. Evaluating the Role of Breast Ultrasound in Early Detection of Breast Cancer in Low- and Middle-Income Countries: A Comprehensive Narrative Review. Bioengineering 2024, 11, 262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, J.; Pian, L.; Chen, J.; Zhao, J.; Liu, Y.; Meng, F.; Zeng, C. Artificial intelligence in breast ultrasound: A systematic review of research advances. Front. Oncol. 2025, 15, 1619364. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parvin, S.; Rozario, L.J.; Islam, M.E. Artificial intelligence in breast cancer diagnosis: A systematic review of imaging modalities, methods, and datasets. Inform. Med. Unlocked 2026, 64, 101786. [Google Scholar] [CrossRef] [Scilit]
- Ali, A.; Alghamdi, M.; Marzuki, S.S.; Tengku Din, T.A.D.A.A.; Yamin, M.S.; Alrashidi, M.; Alkhazi, I.S.; Ahmed, N. Exploring AI Approaches for Breast Cancer Detection and Diagnosis: A Review Article. Breast Cancer Targets Ther. 2025, 17, 927–947. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghauth, K.I.; Kustiawan, Y.A. Explainable Artificial Intelligence (XAI) for Cancer Classification in Medical Imaging: A Systematic Review. Mach. Learn. Knowl. Extr. 2026, 8, 134. [Google Scholar] [CrossRef] [Scilit]
- Dang, C.; Qi, Z.; Xu, T.; Gu, M.; Chen, J.; Wu, J.; Lin, Y.; Qo, X. Deep Learning-Powered Whole Slide Image Analysis in Cancer Pathology. Lab. Investig. 2025, 105, 104186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rad, M.S.; Huang, J.; Hosseini, M.M.; Choudhary, R.; Siezen, H.; Akabari, R.; Jamaspishvili, T.; El-Zammar, O.; Patel, P.G.; Carello, S.J.; et al. Deep learning for digital pathology: A critical overview of methodological framework. J. Pathol. Inform. 2025, 19, 100514. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Datwani, S.; Khan, H.; Niazi, M.K.K.; Parwani, A.V.; Li, Z. Artificial intelligence in breast pathology: Overview and recent updates. Hum. Pathol. 2025, 162, 105819. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chaurasia, A.K.; Toohey, P.W.; Bennett, M.T.; Harris, H.C.; Hewitt, A.W. Automated quantification of Ki-67 expression in breast cancer from H&E-stained slides using a transformer-based regression model. Breast Cancer Res. 2025, 27, 206. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fedoriw, Y.; Silva, O.; Znaor, A.; Macintyre, E. Global view of haematolymphoid tumor classifications and their application in low- and middle-income countries. Histopathology 2025, 86, 6–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alaggio, R.; Amador, C.; Anagnostopoulos, I.; Attygalle, A.D.; Araujo, I.B.d.; Berti, E.; Bhagat, G.; Borges, A.M.; Boyer, D.; Calaminici, M.; et al. The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Lymphoid Neoplasms. Leukemia 2022, 36, 1720–1748. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manescu, P.; Narayanan, P.; Bendkowski, C.; Elmi, M.; Claveau, R.; Pawar, V.; Brown, B.J.; Shaw, M.; Rao, A.; Fernandez-Reyes, D. Detection of acute promyelocytic leukemia in peripheral blood and bone marrow with annotation-free deep learning. Sci. Rep. 2023, 13, 2562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zuromski, L.M.; Durtschi, J.; Aziz, A.; Chumley, J.; Dewey, M.; English, P.; Morrison, M.; Simmon, K.; Whipple, B.; O’Fallon, B.; et al. Clinical validation of a real-time machine learning-based system for the detection of acute myeloid leukemia by flow cytometry. Cytom. Part B Clin. Cytom. 2025, 108, 392–403. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chipidza, F.E.; Kayembe, M.K.A.; Nkele, I.; Efstathiou, J.A.; Chabner, B.A.; Abramson, J.; Dryden-Peterson, S.L.; Sohani, A.R. Accuracy of Pathologic Diagnosis in Patients With Lymphoma and Survival: A Prospective Analysis From Botswana. JCO Glob. Oncol. 2021, 7, 1620–1632. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naresh, K.N.; Raphael, M.; Ayers, L.; Hurwitz, N.; Calbi, V.; Rogena, E.; Sayed, S.; Sherman, O.; Ibrahim, H.A.H.; Lazzi, S.; et al. Lymphomas in sub-Saharan Africa—What can we learn and how can we help in improving diagnosis, managing patients and fostering translational research? Br. J. Haematol. 2011, 154, 696–703. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tellez, D.; Litjens, G.; Bandi, P.; Bulten, W.; Bokhorst, J.-M.; Ciompi, F.; van der Laak, J. Quantifying the effects of data augmentation and stain color normalization in convolutional neural networks for computational pathology. Med. Image Anal. 2019, 58, 101544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, Y.N.; Peng, X.C.; Ma, S.; Yu, H.; Jin, Y.-B.; Zheng, J.; Fu, G.-H. Development of Whole Slide Imaging on Smartphones and Evaluation With ThinPrep Cytology Test Samples: Follow-Up Study. JMIR mHealth uHealth 2018, 6, e82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kenya Association of Radiologists. The Hidden Physician: Understanding the Vital Role of Radiologists. Available online: https://kar.co.ke/blogs/the-radiologist-you-may-never-meet-but-whose-expertise-your-life-depends-on (accessed on 30 July 2026).
- Pang, J.; Xiu, W.; Ma, X. Application of Artificial Intelligence in the Diagnosis, Treatment, and Prognostic Evaluation of Mediastinal Malignant Tumors. J. Clin. Med. 2023, 12, 2818. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tangruangkiat, S.; Chaiwongkot, N.; Pamarapa, C.; Rawangwong, T.; Khunnarong, A.; Chainarong, C.; Sathapanawanthana, P.; Hiranrat, P.; Keerativittayayut, R.; Sungkarat, W.; et al. Diagnosis of focal liver lesions from ultrasound images using a pretrained residual neural network. J. Appl. Clin. Med. Phys. 2023, 25, e14210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Endo, H.; Hirata, K.; Takenaka, J.; Tang, M.; Watanabe, S.; Kimura, R.; Kudo, K. Evaluation of 2D and 3D nnU-Net models with two-label and three-label strategies for automatic segmentation and total metabolic tumor volume estimation of metastatic differentiated thyroid carcinoma on FDG-PET/CT. Jpn. J. Radiol. 2026, 44, 1685–1697. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abdihamid, O.; Affey, F.; Maina, J.; Ngaruiya, C. The current state of oncological emergency services in Kenya: Challenges and opportunities. BMJ Glob. Health 2026, 11, e020895. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smine, Z.; Poeta, S.; De Caluwé, A.; Desmet, A.; Garibaldi, C.; Boni, K.B.; Levillain, H.; Gestel, D.V.; Reynaert, N.; Dhont, J. Automated segmentation in planning-CT for breast cancer radiotherapy: A review of recent advances. Radiother. Oncol. 2025, 202, 110615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moran, K.; Poole, C.; Barrett, S. Evaluating deep learning auto-contouring for lung radiation therapy: A review of accuracy, variability, efficiency and dose, in target volumes and organs at risk. Phys. Imaging Radiat. Oncol. 2025, 33, 100736. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bani, M.A. Smart Lies and Sharp Eyes: Pragmatic Artificial Intelligence for Cancer Pathology: Promise, Pitfalls, and Access Pathways. Cancers 2026, 18, 421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghaffari Laleh, N.; Muti, H.S.; Loeffler, C.M.L.; Echle, A.; Saldanha, O.L.; Mahmood, F.; Lu, M.Y.; Trautwein, C.; Langer, R.; Dislich, B.; et al. Benchmarking weakly-supervised deep learning pipelines for whole slide classification in computational pathology. Med. Image Anal. 2022, 79, 102474. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.