


Highlights
What are the main findings?
- Hospitals that sustained Baby-Friendly designation had consistently higher mPINC survey scores than hospitals that were never designated or lost designation, and late adopters had the largest improvement in scores over time.
- Loss of Baby-Friendly designation was associated with significant decreases in evidence-based practice, as measured by the mPINC survey, including key breastfeeding-supportive domains of immediate postpartum care, feeding practices, and institutional management.
What are the implications of the main findings?
- Sustained Baby-Friendly designation may provide an important accountability structure for maintaining evidence-based maternity care practices, and the loss of designation is associated with lower levels of breastfeeding support.
- Public health and quality-improvement investments that help hospitals to maintain, obtain, or regain Baby-Friendly designation are needed to ensure access to critical breastfeeding support services and evidence-based care.
Abstract
Background/Objectives: Evidence-based maternity care practices supportive of breastfeeding are critical for breastfeeding initiation, exclusivity, and continuation, and these practices are operationalized through the Baby-Friendly Hospital Initiative (BFHI) Ten Steps to Successful Breastfeeding. This study examined longitudinal trajectories of evidence-based maternity care practices supportive of breastfeeding by Baby-Friendly designation status among U.S. hospitals. Methods: Hospital-level data from the Centers for Disease Control and Prevention’s Maternity Practices in Infant Nutrition and Care (mPINC) surveys from 2018, 2020, 2022, and 2024 were analyzed. Hospitals completing at least two surveys were included in the analysis, categorized as having sustained designation, adopted designation late, lost designation, or never been designated. Longitudinal mixed-effects models estimated changes in total and domain-specific mPINC scores over time. Results: Among 2304 hospitals, 400 sustained Baby-Friendly designation, 190 adopted designation late, 160 lost designation, and 1554 were never designated. Hospitals with sustained designation maintained consistently high total mPINC scores from 2018 to 2024. Late adopters improved substantially, increasing 8.9 points (95% CI: 7.0,10.9), whereas hospitals that lost designation declined from 88.1 to 84.7, a change of −3.4 points (95% CI: −5.6, −1.3). Declines among hospitals that lost designation were most evident in immediate postpartum care, feeding practices, and institutional management domains. Never-designated hospitals’ scores improved modestly but remained below those of the sustained Baby-Friendly hospitals across survey years and domains. Conclusions: Sustained Baby-Friendly designation was associated with stable, high implementation of breastfeeding-supportive maternity practices, whereas loss of designation was associated with measurable declines in key breastfeeding-supportive domains. Maintaining or regaining designation may protect access to critical breastfeeding support services across communities.
1. Introduction
Breastfeeding is the normative pattern of infant feeding, supporting infant growth, development, and maternal postpartum recovery and conferring well-established maternal and infant health benefits: breastfeeding provides optimal infant nutrition that is associated with reduced risks of respiratory infections, otitis media, gastrointestinal illness, type 1 diabetes, and sudden infant death syndrome, while also reducing maternal risks of breast and ovarian cancers, type 2 diabetes, and hypertension [1,2,3]. Major medical and public health organizations in the United States (US) recommend exclusive breastfeeding for six months with continued breastfeeding for two years or beyond as long as mutually desired by mother and child [4,5,6,7,8]. The maternity care practices of immediate, uninterrupted skin-to-skin contact, early initiation of breastfeeding, avoidance of non-medically indicated supplementation, and 24 h rooming-in have been shown to enable higher rates of breastfeeding initiation, exclusivity, and duration [9,10,11].
These practices are operationalized in the Baby-Friendly Hospital Initiative (BFHI) Ten Steps to Successful Breastfeeding. The Ten Steps include policies and clinical practices that protect, promote, and support breastfeeding across the prenatal, intrapartum, and immediate postpartum period [12,13]. In the US, Baby-Friendly USA, a national non-profit organization, serves as the accrediting body for the BFHI. Baby-Friendly designation via BFUSA is a key mechanism for advancing evidence-based maternity care practices aligned with the Ten Steps, and adherence to these practices is associated with higher exclusive breastfeeding rates and improved maternal–infant health outcomes [14,15,16]. Yet maintaining designation as a Baby-Friendly hospital requires time and resources, as hospitals must undergo reassessment every five years, and staff turnover and resource constraints contribute to uneven implementation and occasional loss of designation [17,18]. National surveillance indicators suggest that Baby-Friendly hospital designation has decreased from a level representing 29% of U.S. births in 2021 [19] to 22% in 2025 [12]. Re-designation is a critical accountability and sustainability checkpoint, and loss of designation may signal erosion of evidence-based maternity care practices that support optimal breastfeeding.
Since 2007, the Centers for Disease Control and Prevention (CDC) has tracked maternity practices and policies that support breastfeeding through the Maternity Practices in Infant Nutrition and Care (mPINC) survey. Administered approximately every two years, mPINC assesses evidence-based maternity care practices consistent with the Ten Steps such as immediate postpartum care, rooming-in, feeding education and support, and institutional policies [20]. Multiple national analyses have demonstrated a relationship between higher mPINC scores and exclusive breastfeeding rates across survey cycles [21,22,23]. Despite this evidence linking maternity practices to improved breastfeeding outcomes, it remains unknown whether hospitals that lose Baby-Friendly designation subsequently experience declines in maternity practices supportive of breastfeeding compared with hospitals that sustain designation over time.
The objective of this study was to assess whether maternity care practices supportive of breastfeeding differed longitudinally among hospitals with different Baby-Friendly designation status. We used hospital-level data from four mPINC survey cycles to examine changes in overall and domain-specific scores over time by Baby-Friendly designation status.
2. Materials and Methods
2.1. Data Source and Study Sample
For this analysis, we used hospital-level data from the CDC mPINC surveys administered in 2018, 2020, 2022, and 2024. For each survey cycle, the CDC contacts hospitals and asks the mother–baby nurse manager or labor and delivery manager to identify the staff member most knowledgeable about infant feeding practices and maternity care policies to complete the survey [24]. Across these four cycles, mPINC surveys from 2746 unique hospitals were available with 2045 hospitals participating in 2018, 2103 in 2020, 1994 in 2022, and 2070 in 2024 (and response rates of 70%, 75%, 72%, and 78%, respectively [25]. To evaluate longitudinal changes in maternity care practices and Baby-Friendly designation status, we restricted the analytic sample to the 2370 hospitals from across the U.S. that completed at least two mPINC surveys between 2018 and 2024. This study was determined to be exempt from review by the Institutional Review Board at the Pacific Institute for Research and Evaluation (IRB #2314171-1).
2.2. Measurement
The survey includes six core domains that assess hospital maternity care practices associated with breastfeeding outcomes. These domains include (1) Immediate postpartum care; (2) Rooming-in; (3) Feeding practices; (4) Feeding education and support; (5) Discharge support; and (6) Institutional management (comprising staff training, breastfeeding data collection, formula acquisition, and policies related to breastfeeding) [20]. The total mPINC score indicates a hospital’s overall alignment with evidence-based maternity care practices that support optimal infant feeding, and it is the average of the six domain scores. Scores range from 0 to 100, with higher scores indicating greater alignment with supportive practices.
In this analysis, the primary outcome was the hospital’s total mPINC score for each survey year, and it was used to examine differences in maternity care practices by hospital Baby-Friendly USA designation status. Domain-specific scores were also analyzed to characterize which areas of maternity care practice contributed to observed differences in the total score and to inform potential targets for quality improvement. Domain-specific scores were not calculated if half or more of the items within that domain were did not have a score. The total mPINC score was not calculated if any domain score was missing, consistent with CDC scoring guidance.
Baby-Friendly designation status was determined using mPINC item A3 for each survey year: “Is your hospital currently designated as ‘Baby-Friendly’ by the Baby-Friendly Hospital Initiative (BFHI)?”. For each hospital, designation status was assessed across all completed survey years to characterize longitudinal designation trajectories. Hospitals were categorized into four mutually exclusive longitudinal designation cohorts based on monotonic designation patterns across completed survey years: (1) Never designated: not designated in any completed survey year; (2) Sustained designation: designated in all completed survey years; (3) Lost designation: transitioned from designated to not designated without subsequently regaining designation; and (4) Adopted late: transitioned from not designated to designated without subsequently losing designation. Hospitals with non-monotonic designation trajectories were excluded from cohort analyses (N = 66). Cohort assignment was based solely on the survey waves each hospital completed; designation status was not imputed for non-completed waves.
Hospital characteristics, including hospital ownership type, teaching hospital status, highest level of neonatal care, geographic region, and hospital size (via annual live births) were used for descriptive and adjusted analyses. Characteristics reflect the most recent available mPINC survey response for each hospital.
2.3. Statistical Analyses
We built a longitudinal mixed-effects model to examine change in total and domain-specific mean mPINC scores over time by Baby-Friendly designation cohort. We compared a linear time specification with a categorical time specification using the Akaike Information Criterion (AIC). The categorical-time model demonstrated substantially better fit, indicating non-linear change in scores across years. Therefore, time was represented using indicator variables for survey year (2018, 2020, 2022, and 2024), allowing for flexible, non-linear changes in mPINC scores over time.
Models included a hospital-level random intercept to account for clustering of repeated measures within hospitals and an autoregressive correlation structure to account for within-hospital temporal correlation. Using categorical time models, we estimated predicted mean total and domain-specific mPINC scores for each cohort–year combination, and contrasts were used to estimate within-cohort change from 2018 to 2024 as well as between-cohort differences at each time point. Statistical significance was evaluated using two-sided tests with α = 0.05. All differences were expressed as the difference between 2024 and 2018 to preserve temporal interpretation and ensure consistent directionality of change.
To assess potential confounding, we sequentially adjusted the primary mixed-effects model by each of the hospital characteristics described above using the most recent survey response available for each hospital. Across all adjusted models, effect estimates for Baby-Friendly designation cohort and survey year differed by less than 5% from the base model after adjustment, with no changes in direction or statistical significance. Therefore, hospital characteristics were not retained in the final models to preserve parsimony.
3. Results
A total of 2304 maternity hospitals were included in the analysis, including 400 hospitals that sustained Baby-Friendly designation, 190 that adopted designation late, 160 that lost designation, and 1554 that were never designated (Table 1). Hospitals that sustained designation were more likely to be government or military institutions and teaching hospitals compared with facilities that were never Baby-Friendly. Hospitals that sustained designation also tended to have higher levels of neonatal care and larger delivery volumes. In contrast, hospitals that were never designated were more commonly smaller-volume, for-profit, private hospitals and more frequently reported lower levels of neonatal care. Regional distribution varied modestly across cohorts, with sustained designation hospitals somewhat more concentrated in the Northeast and Western regions compared with hospitals that were never designated (Table 1).
Table 1.
Descriptive Characteristics of Maternity Hospitals by Baby-Friendly Designation Cohort.
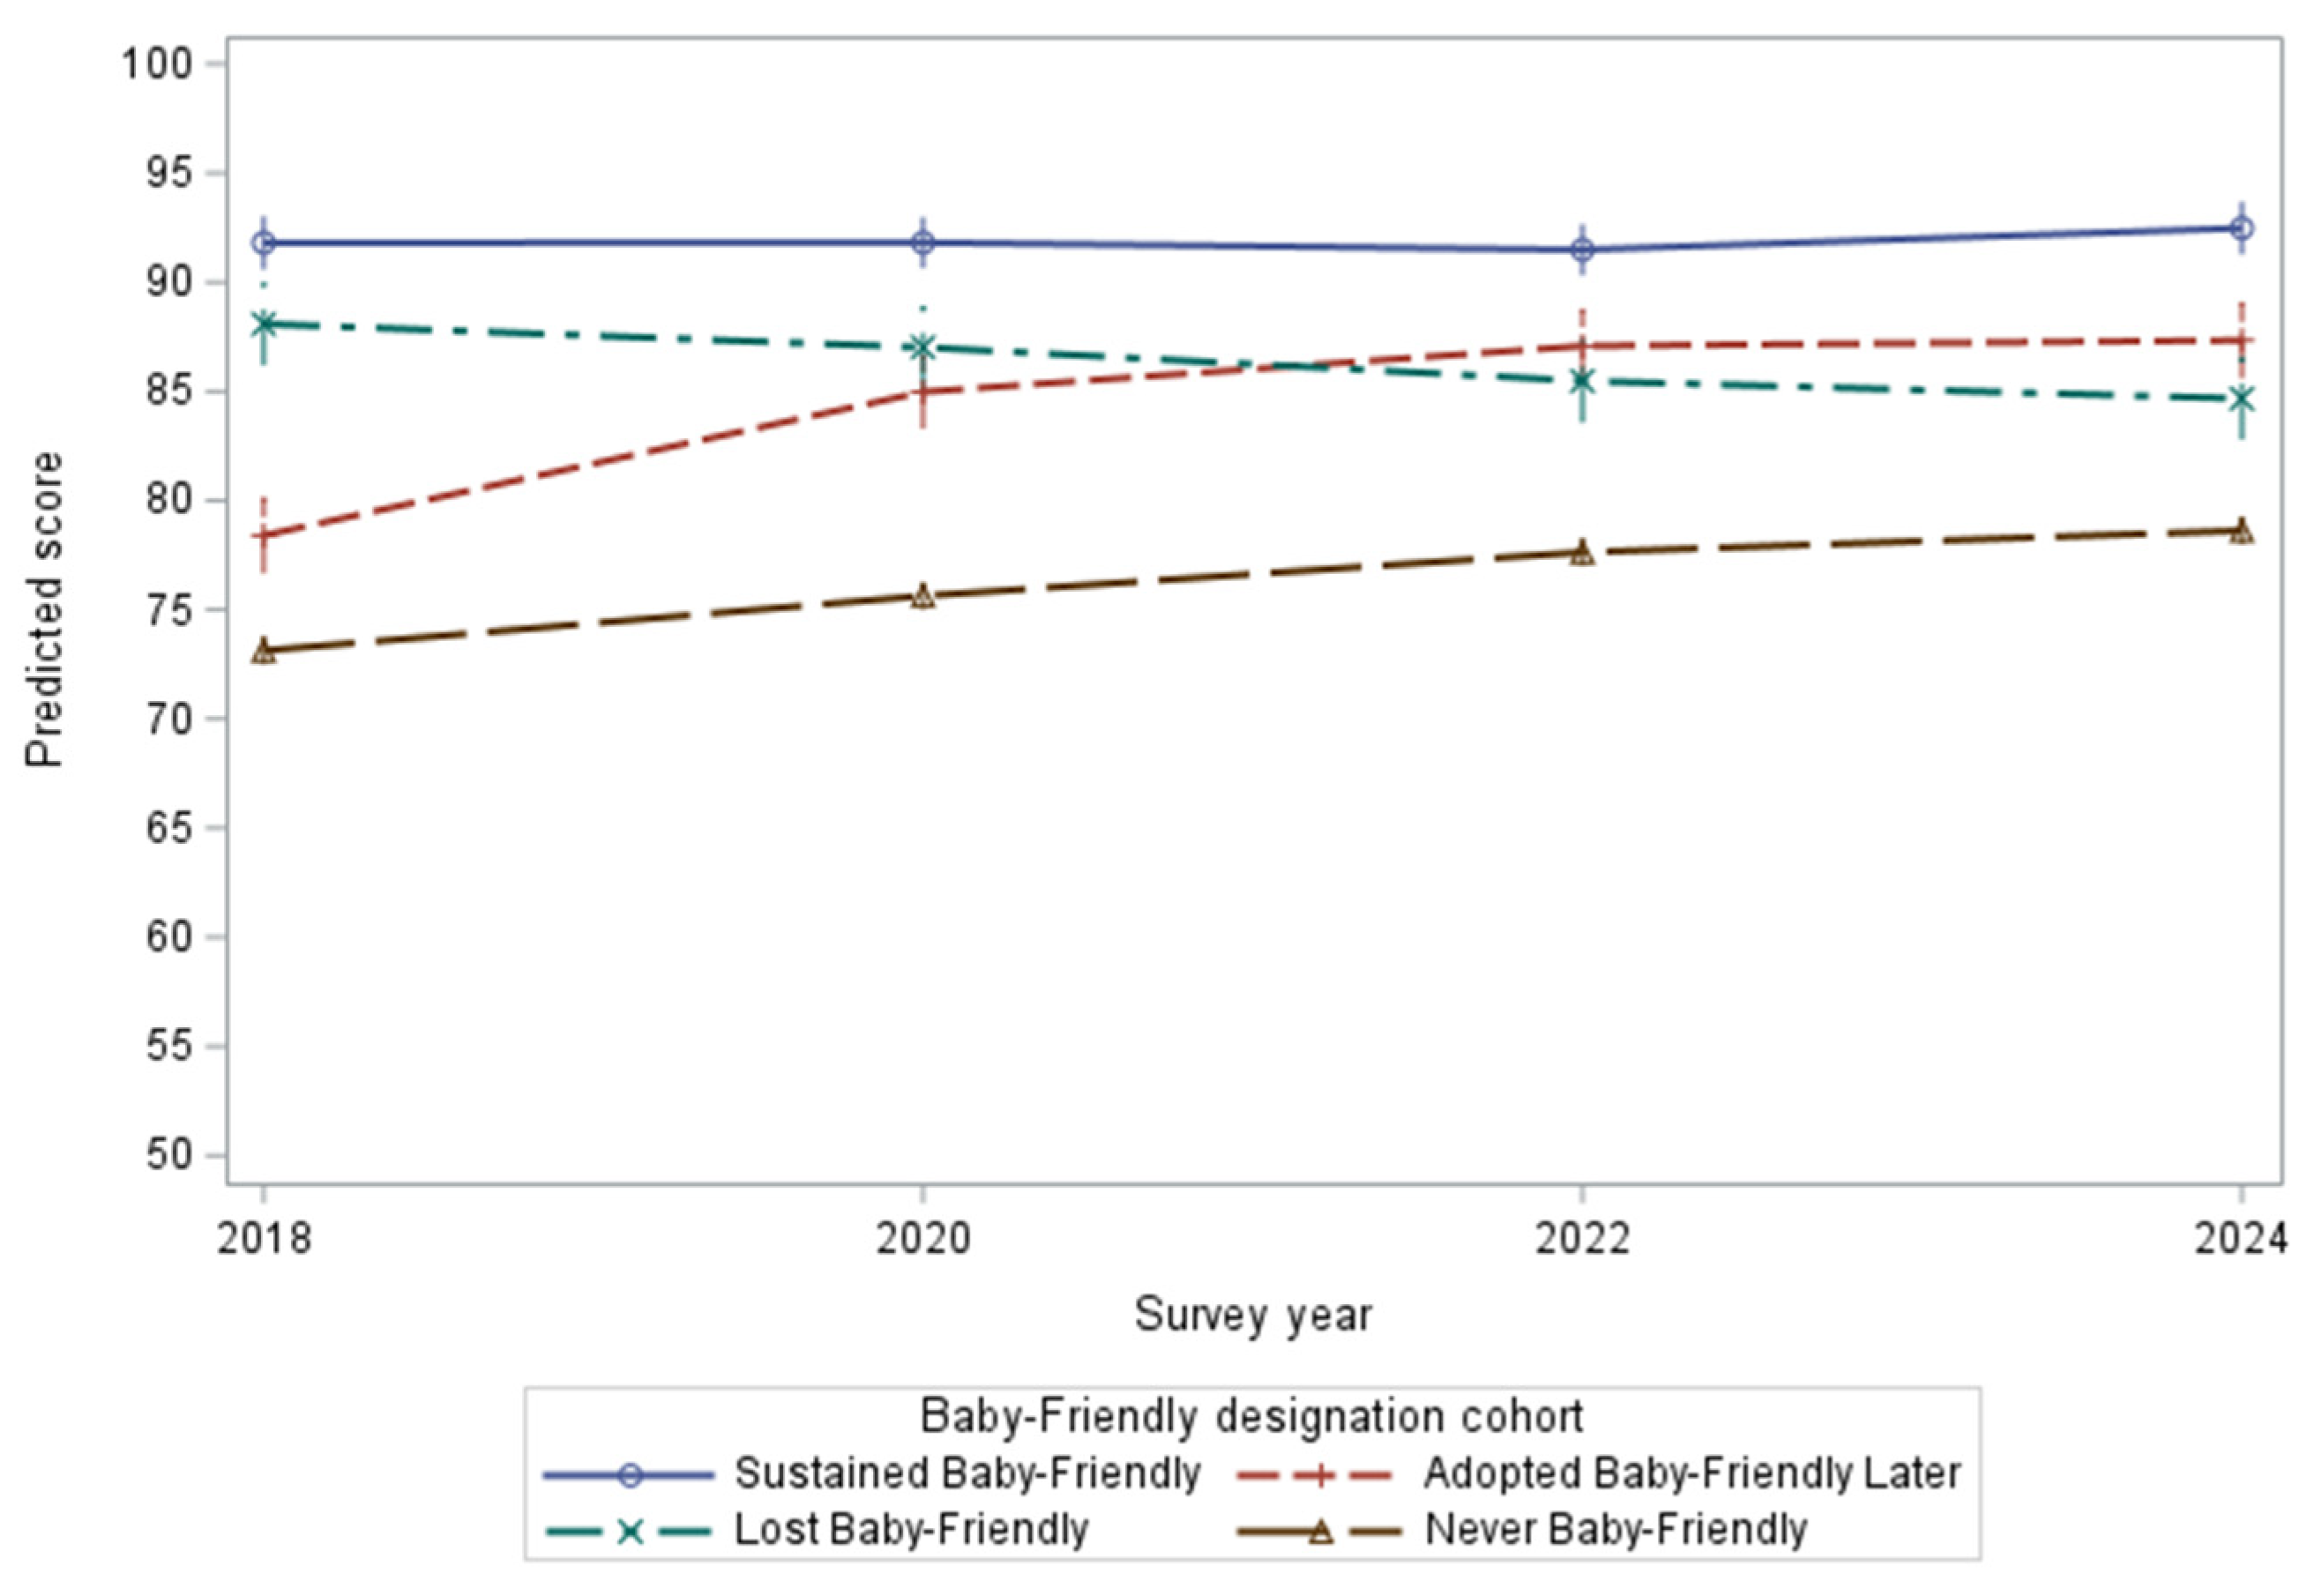
Predicted total mPINC scores changed significantly over time within most hospital cohorts except for the sustained cohort, where they remained basically stable over time. Between 2018 and 2024, “Adopted late” hospitals increased by 8.9 points (95% CI: 7.0, 10.9), hospitals that lost designation declined by 3.4 points (95% CI: −5.6, −1.3), and “No designation” hospitals increased by 5.5 points (95% CI: 4.8, 6.2) (Table 2).
Table 2.
Predicted total and domain-specific mPINC scores by Baby-Friendly designation cohort, 2018–2024.
Across the 2018–2024 surveys, predicted scores were consistently highest among hospitals with sustained Baby-Friendly designation, followed by those that adopted designation later, those that lost designation, and finally hospitals that were never designated. Total mPINC scores remained stable and high among sustained Baby-Friendly hospitals, increased over time among late adopters, and remained lower but increasing over time among never-designated hospitals, while scores among hospitals that lost designation declined modestly, diverging from the background trajectory (Figure 1).
Figure 1.
Total mPINC score by Baby-Friendly designation cohort, 2018–2024.
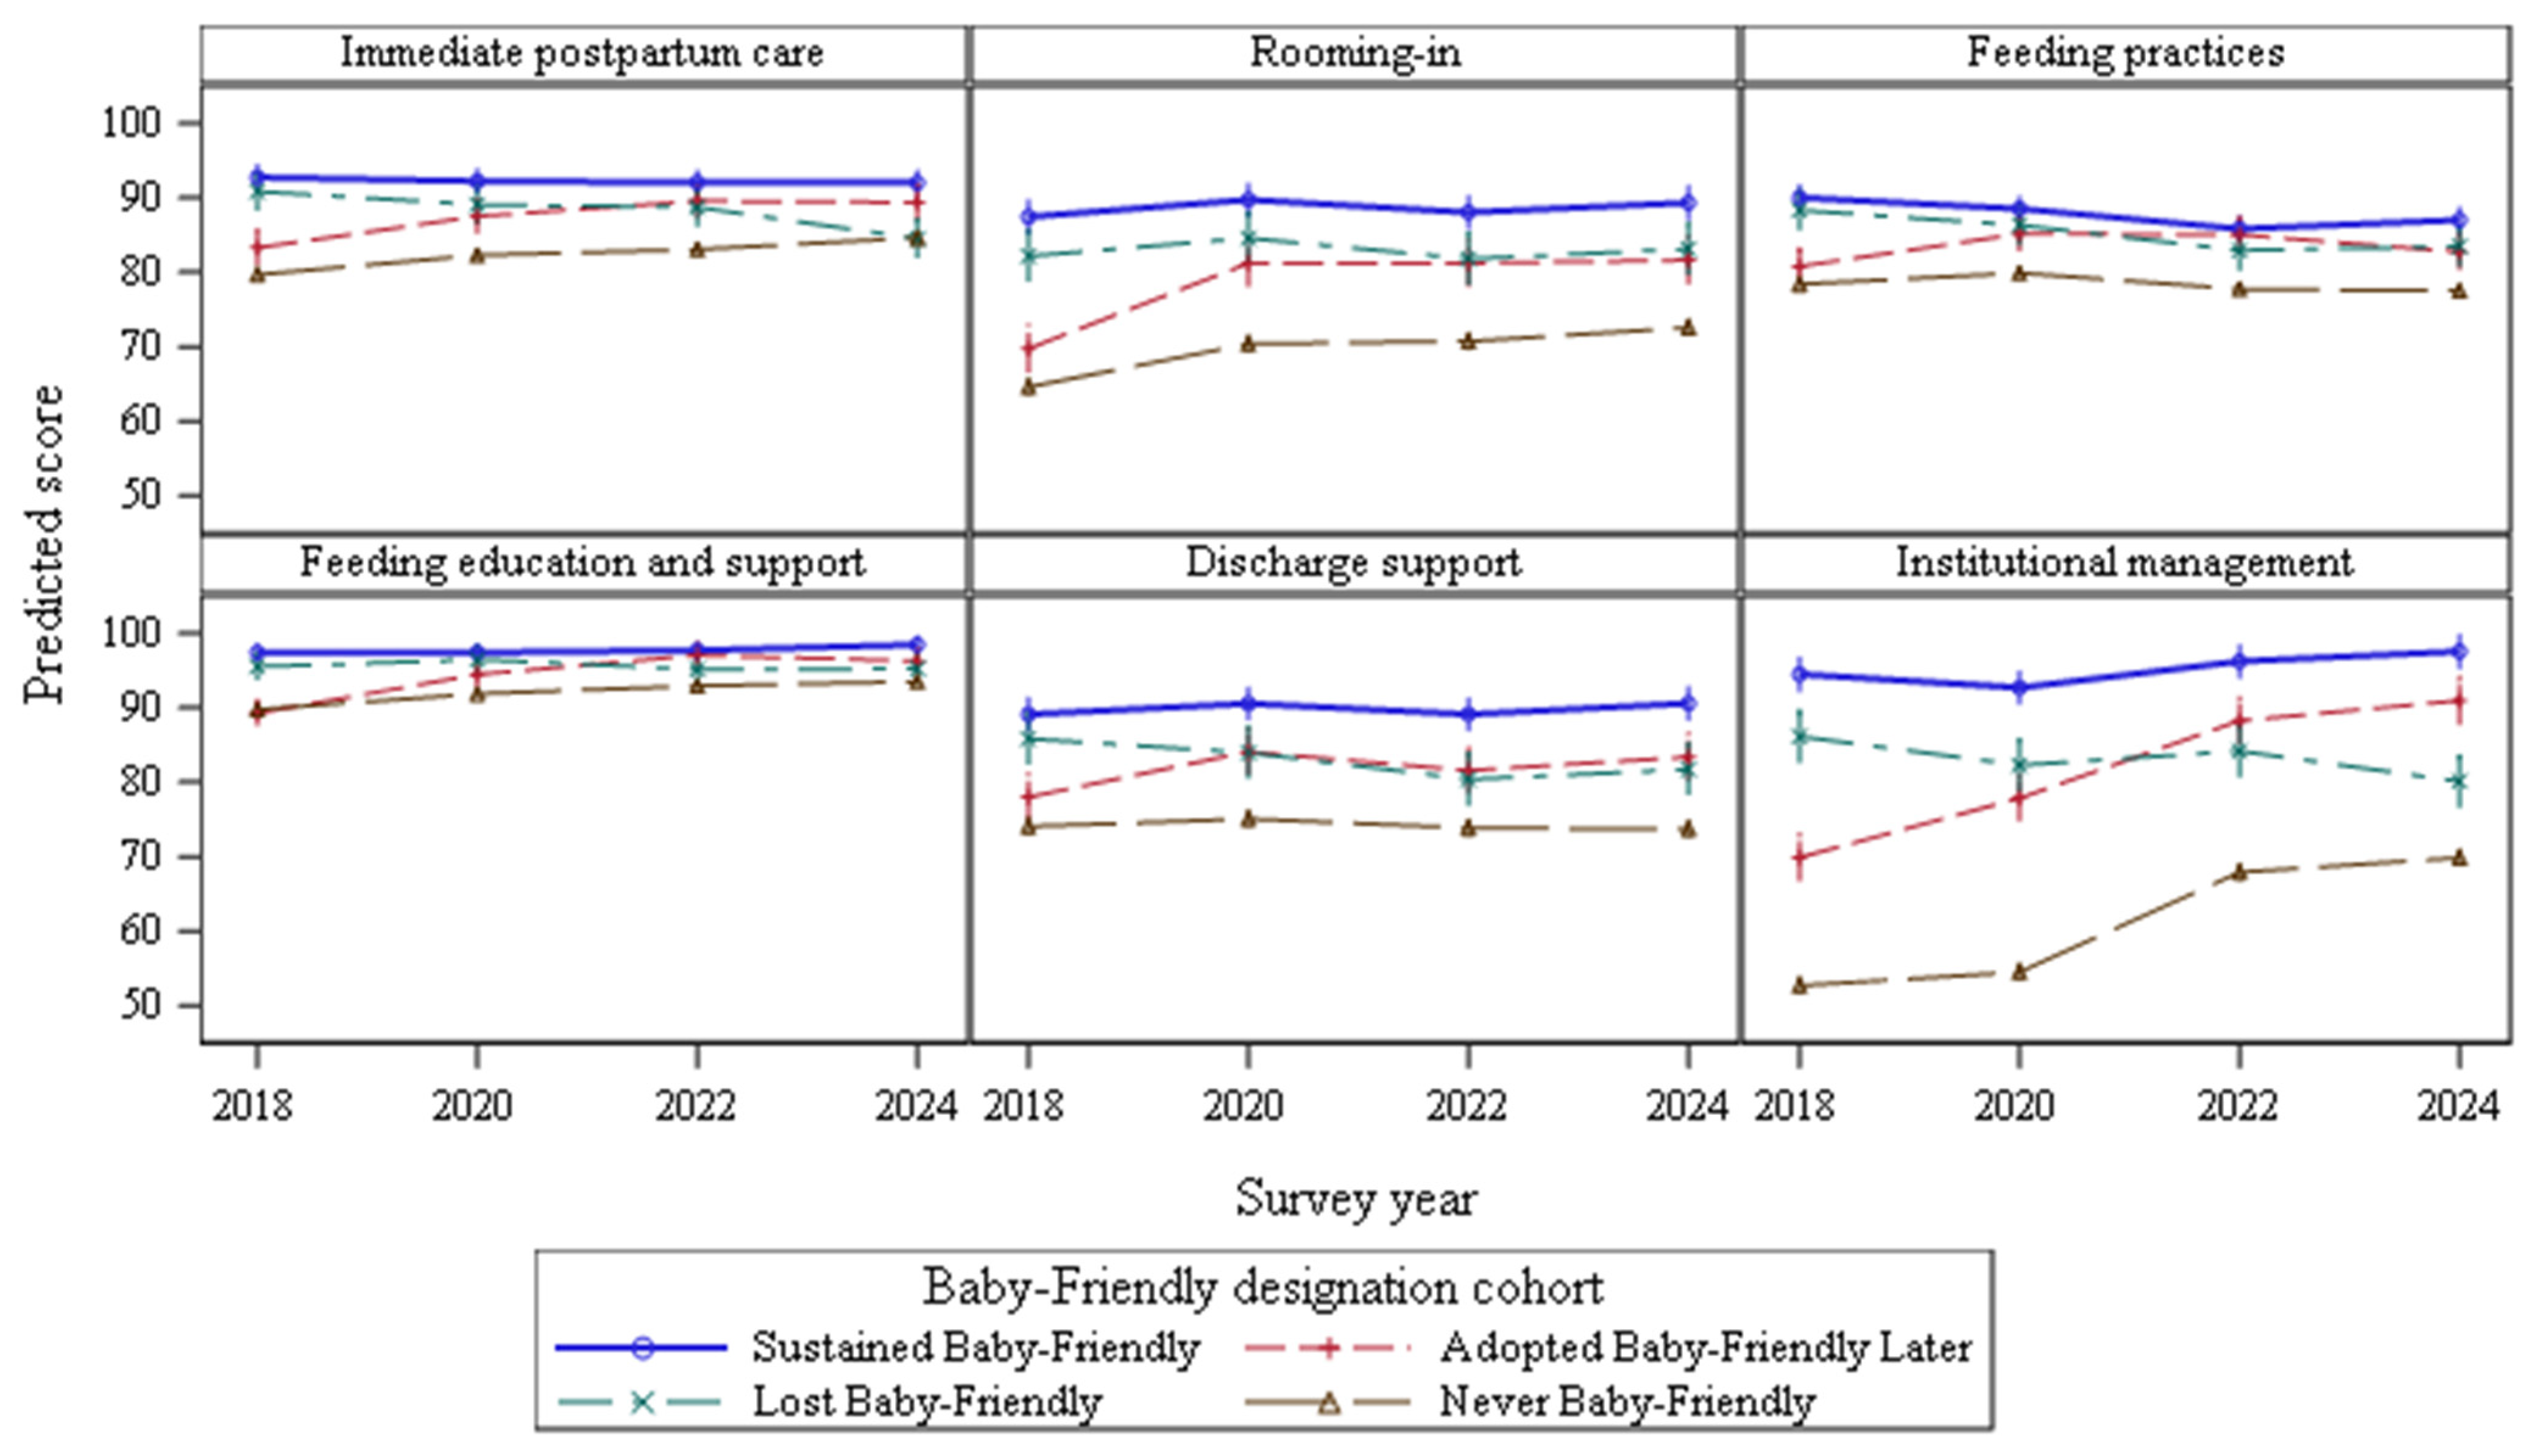
Domain-specific patterns were similar, with the largest improvements observed among late adopters in institutional management and rooming-in, and persistently lower scores among never-designated hospitals across all domains. Differences between cohorts were most pronounced in institutional management, discharge support, and rooming in, whereas gaps were narrower for immediate postpartum care, feeding education and support, and feeding practices (Figure 2).
Figure 2.
Domain-specific mPINC scores by Baby-Friendly designation cohort, 2018–2024.
4. Discussion
In this longitudinal analysis of U.S. hospitals participating in multiple mPINC survey cycles from 2018 through 2024, hospitals that sustained Baby-Friendly designation maintained consistently high levels of evidence-based maternity care practices supportive of breastfeeding, while hospitals that lost designation experienced significant declines overall and in key domains central to breastfeeding support, including immediate postpartum care, feeding practices, and institutional management. These findings demonstrate longitudinal associations between Baby-Friendly designation status and maternity care practices as measured through the mPINC survey. Out of a 100-point total mPINC score, hospitals that sustained Baby-Friendly designation maintained total scores above 90 across the study period (91.5–92.5), while hospitals that adopted designation later demonstrated substantial improvements over time, with scores increasing from 78.4 to 87.3. In contrast, hospitals that lost designation had significant declines in total mPINC scores, and hospitals that were never designated had mPINC scores that remained about 14 points below those of hospitals with sustained designation. Given that a 10-point increase in a modified mPINC score is associated with a 4.4 percentage point increase in exclusive breastfeeding [21], these sizable mPINC score differences by Baby-Friendly designation status highlight the potential importance of structured public health programs that improve maternal and infant health outcomes.
The practices captured by mPINC are closely aligned with the Ten Steps and with the clinical processes through which hospitals support breastfeeding initiation, exclusivity, and continuation [21,26]. The decline for hospitals that lost designation was evident not only in the total score, but also in domains central to both bedside care and the organizational infrastructure that sustains it. Declines in immediate postpartum care and feeding practices are particularly consequential given the established links between skin-to-skin contact, avoidance of non-medically indicated supplementation, and breastfeeding outcomes [27,28,29]. Beyond breastfeeding outcomes, reduced implementation of these practices may also have consequences for maternal caregiving capacity, particularly among the most vulnerable mothers [30]. The parallel decline in institutional management, reflecting staff training, breastfeeding data monitoring, and policy infrastructure (see Section 2.2), suggests that loss of designation may weaken bedside practice and the administrative systems that sustain them over time. With most mothers in the U.S. initiating breastfeeding (86.1% for infants born in 2023 [19], maintaining this infrastructure across all hospitals may help families reach their infant feeding goals.
The pattern among late-adopting hospitals provides additional evidence that adoption of Baby-Friendly designation is associated with meaningful improvements in measured practices. Late adopters began the study period with lower total and domain-specific scores than sustained Baby-Friendly hospitals but showed large gains by 2024, particularly in institutional management and rooming-in. These domains reflect hospital-level policies, staff responsibilities, and care routines that often require system-level change rather than isolated clinical education. Their improvement among late adopters is consistent with the interpretation that Baby-Friendly implementation may contribute to organizational change when hospitals make active investments in policy, training, monitoring, and workflow redesign. At the same time, late adopters did not reach the consistently high performance observed among hospitals that sustained designation throughout the study period, reinforcing the potential importance of continued monitoring and reassessment after initial gains are achieved.
Findings from this study are consistent with prior research showing that Baby-Friendly implementation is associated with more breastfeeding-supportive hospital care. Two recent systematic review and meta-analyses found that Baby-Friendly implementation was associated with improved early initiation of breastfeeding and exclusive breastfeeding at later time points, although effect sizes varied by context and implementation fidelity [31,32]. Alongside our findings, this literature suggests that the benefits of Baby-Friendly designation may depend not only on initial implementation, but also on sustained adherence, staff competency, and institutional reinforcement over time.
Differences in hospital characteristics across designation cohorts also have implications for access to breastfeeding supportive care. Patterson et al. found that Baby-Friendly designation is associated with increases in exclusive breastfeeding in hospitals located across all neighborhood socioeconomic levels [16]. This finding is particularly consequential because breastfeeding rates are lower among socioeconomically disadvantaged women, leaving their infants disproportionately exposed to the health risks associated with reduced or absent breastfeeding [33]. Targeted expansion of Baby-Friendly designation may help narrow this exposure gap and reduce the disproportionate burden of preventable infant morbidity among disadvantaged communities [34]. In our study, hospitals sustaining Baby-Friendly designation tended to be larger, higher-acuity, and more often teaching institutions, whereas hospitals that were never designated were more commonly smaller-volume and for-profit hospitals with lower levels of neonatal care. Although adjustment for measured hospital characteristics did not materially change our estimates, these descriptive differences suggest that the capacity to achieve and maintain Baby-Friendly designation may be unevenly distributed across the maternity care system [35]. If smaller-volume hospitals or those operating with fewer resources are less likely to sustain evidence-based practices supportive of breastfeeding, women giving birth in those settings may have less reliable access to breastfeeding-supportive care. Sustained investment in technical assistance, staff training, and quality-improvement infrastructure may be necessary to ensure that the benefits of Baby-Friendly-aligned maternity care are available across diverse hospital settings.
4.1. Limitations
The findings should be interpreted within the context of several limitations. First, mPINC data are self-reported by hospital staff and may be subject to reporting bias. Second, Baby-Friendly designation status was measured using the mPINC survey item rather than independently verified designation records for each year, which could introduce misclassification. Third, the designation cohorts were defined using completed survey waves; hospitals with non-monotonic designation trajectories were excluded from cohort analyses, and survey nonresponse may have influenced observed patterns. Fourth, our study evaluated hospital practices and policies rather than patient-level breastfeeding outcomes, so the analysis cannot directly estimate the effect of designation loss on breastfeeding initiation, exclusivity, or duration. Finally, although measured hospital characteristics did not meaningfully confound the main estimates, unmeasured factors such as leadership commitment, staffing models, lactation consultant availability, local breastfeeding coalitions, and state policy environments may have influenced both designation trajectories and mPINC scores.
Cohort classification relied on observed designation status at completed survey waves only; for hospitals that did not complete all four surveys, designation status during intervening, non-completed waves is unknown. It is possible that some hospitals classified as Sustained or Never Designated experienced an undetected change in status during an unobserved wave, which could not be captured by our monotonic classification rule, though when we re-estimated the primary model restricted to the hospitals that completed all four survey waves, there were no significant changes in point estimates and 95% confidence intervals, suggesting our findings are unlikely to be explained by incomplete survey participation. For hospitals classified as Adopted Late or Lost Designation, the observed transition in designation status could have occurred at any point within the interval between the two completed survey waves that bracketed it. While this interval was not always a single, consecutive survey cycle, the observed transition did occur in an adjacent two-year survey window for 94% of the Adopted Late hospitals and 86% of the Lost Designation hospitals. This imprecision in the timing of transition is additional limitation of the monotonic classification approach.
4.2. Strengths
This study has also several strengths. We used national hospital-level surveillance data, although the survey is a long-standing national surveillance system collected across four mPINC survey cycles, allowing examination of longitudinal trajectories rather than cross-sectional differences alone. The analytic approach distinguishes hospitals that sustained, adopted, lost, or never achieved designation, providing a more nuanced assessment of Baby-Friendly status than a simple designated versus non-designated comparison. The inclusion of domain-specific scores also helps identify which areas of practice changed most over time and where hospitals may need targeted support. Finally, the use of mixed-effects models accounts for repeated measures within hospitals and allows flexible modeling of non-linear change across survey years.
4.3. Implications
These findings have important implications for public health practice and policy. Sustained Baby-Friendly designation was consistently shown to correspond to high levels of maternity care practices supportive of breastfeeding over time. Loss of Baby-Friendly designation is associated with decreased compliance with recommended maternity practices to support breastfeeding. Re-designation processes, ongoing monitoring, and the external accountability may prevent erosion of practices after initial implementation. At the same time, the lower scores among never-designated hospitals indicate that broader dissemination of Baby-Friendly-aligned practices is critical and consistent with recommendations from the National Academy of Sciences that all U.S. maternity care facilities implement the Ten Steps as the standard of care to meet national breastfeeding objectives and improve health equity [36].
These findings also highlight the need for implementation research focused on why some hospitals are unable to maintain and sustain Baby-Friendly designation. Prior work has noted that loss of Baby-Friendly designation occurs [16] and that additional research is needed to understand the organizational, financial, staffing, and leadership factors that contribute to unsuccessful maintenance [17,37]. Potential mechanisms include staff turnover, reduced leadership engagement, lack of prioritization of staff breastfeeding training and competency, and insufficient internal monitoring after the initial designation period. Future research should examine the reasons hospitals lose designation, identify supports that promote successful re-designation, and link hospital-level designation trajectories to patient-level breastfeeding and equity outcomes.
5. Conclusions
Findings from this longitudinal analysis of national data indicate that loss of Baby-Friendly designation may reduce access to critical breastfeeding support services for women across the communities those hospitals serve. Sustained designation, re-designation, and ongoing quality-improvement support may therefore be important mechanisms for protecting community access to breastfeeding-supportive maternity care. Public health investments that help hospitals maintain or regain Baby-Friendly designation are especially important for ensuring that women and infants across diverse geographic, socioeconomic, and hospital settings have access to evidence-based breastfeeding support.
Author Contributions
Conceptualization, K.W. and E.F.; methodology, K.W.; data cleaning and analysis, K.W.; writing—original draft preparation, K.W.; writing—review and editing, K.W. and E.F. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and determined to be exempt from full review by the Institutional Review Board of the Pacific Institute for Research and Evaluation (ID# 2314171-1, 11 April 2025).
Informed Consent Statement
Since this was not human subject research, signed informed consent form was not required.
Data Availability Statement
Upon request, data with hospital identifiers (i.e., hospital name and address) may be shared under a data use agreement between the Centers for Disease Control and Prevention and applicable state, tribal, local, and territorial health departments for the development of public health programs. Data without hospital identifiers may be released under data use agreements for additional approved purposes such as answering research questions. Email mpinc@cdc.gov to learn more and to receive a data request form.
Acknowledgments
The Centers for Disease Control and Prevention provided hospital data for 2018–2024, as compiled from data provided through the Maternity Practices in Infant Nutrition and Care (mPINC) surveys, in July 2025.
Conflicts of Interest
FitzPatrick is Chief Executive Officer of Baby-Friendly USA. She had no involvement in mPINC data cleaning or analysis, which was conducted by Wouk. The authors declare no remaining conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ACOG | American College of Obstetricians and Gynecologists |
| AIC | Akaike Information Criterion |
| APHA | American Public Health Association |
| BFHI | Baby-Friendly Hospital Initiative |
| CDC | Centers for Disease Control and Prevention |
| CI | Confidence interval |
| IRB | Institutional Review Board |
| mPINC | Maternity Practices in Infant Nutrition and Care |
| NICU | Neonatal intensive care unit |
| US | United States |
| WIC | Special Supplemental Nutrition Program for Women, Infants, and Children |
References
- Victora, C.G.; Bahl, R.; Barros, A.J.; Franca, G.V.; Horton, S.; Krasevec, J.; Murch, S.; Sankar, M.J.; Walker, N.; Rollins, N.C.; et al. Breastfeeding in the 21st century: Epidemiology, mechanisms, and lifelong effect. Lancet 2016, 387, 475–490. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oddy, W.H. Breastfeeding, Childhood Asthma, and Allergic Disease. Ann. Nutr. Metab. 2017, 70, 26–36. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lokossou, G.A.G.; Kouakanou, L.; Schumacher, A.; Zenclussen, A.C. Human Breast Milk: From Food to Active Immune Response With Disease Protection in Infants and Mothers. Front. Immunol. 2022, 13, 849012. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meek, J.Y.; Noble, L. Section on Breastfeeding. Policy Statement: Breastfeeding and the Use of Human Milk. Pediatrics 2022, 150, e2022057988. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- An Update to a Call to Action to Support Breastfeeding: A Fundamental Public Health Issue; APHA: Washington, DC, USA, 2013.
- ACOG Committee Opinion No. 756: Optimizing Support for Breastfeeding as Part of Obstetric Practice. Obstet. Gynecol. 2018, 132, e187–e196. [CrossRef] [Scilit] [PubMed]
- Dietary Guidelines for Americans, 2025–2030; USDA: Washington, DC, USA, 2026.
- Breastfeeding Recommendations and Guidance. Available online: https://www.cdc.gov/breastfeeding/php/guidelines-recommendations/index.html (accessed on 17 August 2026).
- Pérez-Escamilla, R.; Martinez, J.L.; Segura-Pérez, S. Impact of the Baby-friendly Hospital Initiative on breastfeeding and child health outcomes: A systematic review. Matern. Child Nutr. 2016, 12, 402–417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bookhart, L.H.; Anstey, E.H.; Kramer, M.R.; Perrine, C.G.; Ramakrishnan, U.; Young, M.F. A dose-response relationship found between the Ten Steps to Successful Breastfeeding indicators and in-hospital exclusive breastfeeding in US hospitals. Birth 2023, 50, 916–922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- French, C.D.; Shafique, M.A.; Bang, H.; Matias, S.L. Perinatal Hospital Practices Are Associated with Breastfeeding through 5 Months Postpartum among Women and Infants from Low-Income Households. J. Nutr. 2023, 153, 322–330. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baby-Friendly USA. Available online: https://www.babyfriendlyusa.org/ (accessed on 22 September 2026).
- Guideline: Protecting, Promoting, and Supporting Breastfeeding in Facilities Providing Maternity and Newborn Services; World Health Organization: Geneva, Switzerland, 2017.
- Burnham, L.; Knapp, R.; Bugg, K.; Nickel, N.; Beliveau, P.; Feldman-Winter, L.; Merewood, A. Mississippi CHAMPS: Decreasing Racial Inequities in Breastfeeding. Pediatrics 2022, 149, e2020030502. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ducharme-Smith, K.; Gross, S.M.; Resnik, A.; Rosenblum, N.; Dillaway, C.; Orta Aleman, D.; Augustyn, M.; Silbert-Flagg, J.; Caulfield, L.E. Exposure to Baby-Friendly Hospital Practices and Breastfeeding Outcomes of WIC Participants in Maryland. J. Hum. Lact. 2022, 38, 78–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patterson, J.A.; Keuler, N.S.; Buckingham, W.R. Differences in Exclusive Breastfeeding Rates in US Hospitals According to Baby-Friendly Hospital Initiative Designation and Area Deprivation Index Category. Breastfeed. Med. 2021, 16, 799–806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walsh, A.; Pieterse, P.; Mishra, N.; Chirwa, E.; Chikalipo, M.; Msowoya, C.; Keating, C.; Matthews, A. Improving breastfeeding support through the implementation of the Baby-Friendly Hospital and Community Initiatives: A scoping review. Int. Breastfeed. J. 2023, 18, 22. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dennison, B.A.; Nguyen, T.Q.; Gregg, D.J.; Fan, W.; Xu, C. The Impact of Hospital Resources and Availability of Professional Lactation Support on Maternity Care: Results of Breastfeeding Surveys 2009–2014. Breastfeed. Med. 2016, 11, 479–486. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Breastfeeding Among US Children Born 2015–2022, CDC National Immunization Survey-Child; National Center for Chronic Disease Prevention and Health Promotion: Atlanta, GA, USA, 2025.
- Maternity Practices in Infant Nutrition and Care (mPINC) Survey. Available online: https://www.cdc.gov/breastfeeding-data/mpinc/index.html (accessed on 22 September 2026).
- Gosdin, L.; Marks, K.J.; Addo, O.Y.; O’Connor, L.; Awan, S.; Grossniklaus, D.A.; Hamner, H.C. Longitudinal Association of Maternity Care Practices with Exclusive Breastfeeding in U.S. Hospitals, 2018–2022. Children 2025, 12, 1454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barrera, C.M.; Beauregard, J.L.; Nelson, J.M.; Perrine, C.G. Association of Maternity Care Practices and Policies with In-Hospital Exclusive Breastfeeding in the United States. Breastfeed. Med. 2019, 14, 243–248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nelson, J.M.; Grossniklaus, D.A.; Galuska, D.A.; Perrine, C.G. The mPINC survey: Impacting US maternity care practices. Matern. Child Nutr. 2021, 17, e13092. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- mPINC Survey Methods. Available online: https://www.cdc.gov/breastfeeding-data/mpinc/methodology.html (accessed on 22 September 2026).
- mPINC National Report. Available online: https://www.cdc.gov/breastfeeding-data/mpinc/national-report.html (accessed on 22 September 2026).
- Marks, K.J.; Gosdin, L.; O’Connor, L.E.; Hamner, H.C.; Grossniklaus, D.A. Changes in maternity care policies and practices that support breastfeeding as measured by the Ten Steps to Successful Breastfeeding—United States, 2018–2022. BMC Pregnancy Childbirth 2024, 24, 475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daniels, F.; Sawangkum, A.; Kumar, A.; Coombs, K.; Louis-Jacques, A.; Ho, T.T.B. Skin to Skin Contact Correlated with Improved Production and Consumption of Mother’s Own Milk. Breastfeed. Med. 2023, 18, 483–488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moore, E.R.; Brimdyr, K.; Blair, A.; Jonas, W.; Lilliesköld, S.; Svensson, K.; Ahmed, A.H.; Bastarache, L.R.; Crenshaw, J.T.; Giugliani, E.R.J.; et al. Immediate or early skin-to-skin contact for mothers and their healthy newborn infants. Cochrane Database Syst. Rev. 2025, 10, Cd003519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, R.; Hamner, H.C.; Chen, J.; Elam-Evans, L.D. Impact of early formula supplementation on breastfeeding duration, National Immunization Survey, 2019 births. J. Perinatol. 2023, 43, 1176–1178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gribble, K.D. Supporting vulnerable women in mothering through skin-to-skin contact, proximity and breastfeeding: Part 1 research. Breastfeed. Rev. 2024, 32, 6–18. [Google Scholar]
- Habte, M.B.; Abdulahi, M.; Plusquin, M.; Cosemans, C. Effectiveness of Baby-Friendly Hospital Initiative on Early Initiation and Exclusive Breastfeeding Practice: Systematic Review and Meta-Analysis. Nutrients 2025, 17, 2283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fan, Y.W.; Fan, H.S.L.; Shing, J.S.Y.; Ip, H.L.; Fong, D.Y.T.; Lok, K.Y.W. Impact of baby-friendly hospital initiatives on breastfeeding outcomes: Systematic review and meta-analysis. Women Birth 2025, 38, 101881. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quigley, M.A.; Cumberland, P.; Cowden, J.M.; Rodrigues, L.C. How protective is breast feeding against diarrhoeal disease in infants in 1990s England? A case-control study. Arch. Dis. Child. 2006, 91, 245–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lawler, E.C.; Yewell, K.G. The effect of hospital postpartum care regulations on breastfeeding and maternal time allocation. Am. Econ. J. Appl. Econ. 2023, 15, 477–513. [Google Scholar] [CrossRef] [Scilit]
- Tafili, A.; Zakari, N.M.A.; Hamadi, H.Y.; Spaulding, A. Association of hospital and community factors on the attainment of Baby-Friendly designation: A breastfeeding health promotion. Matern. Child Nutr. 2022, 18, e13388. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- National Academies of Sciences, Engineering, and Medicine; Division of Behavioral and Social Sciences and Education; Board on Behavioral, Cognitive, and Sensory Sciences; Board on Children, Youth, and Families; Committee on Understanding Breastfeeding Promotion, Initiation and Support Across the United States. An Analysis. In Breastfeeding in the United States: Strategies to Support Families and Achieve National Goals; Young, M., Caswell, J.A., Asiodu, I., Eds.; National Academies Press (US): Washington, DC, USA, 2025. [Google Scholar]
- Mäkelä, H.; Axelin, A.; Niela-Vilén, H. Journey toward Baby-Friendly Hospital Initiative designation: Healthcare professional’s view on successful implementation process and maintenance of accreditation. Midwifery 2024, 135, 104029. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.