


Abstract
Benign biliary tumors and precursor neoplasms of the biliary tract are a heterogeneous group of uncommon neoplasms with significant clinical and diagnostic implications. Their importance lies in their variable malignant potential and morphological and molecular similarities to pancreatic neoplasms. The sixth edition of the World Health Organization Classification of Digestive System Tumours (WHO DST6), published online in 2026, introduced major revisions to the classification of these entities. According to WHO DST6, benign tumors and precursor neoplasms of the liver and intrahepatic bile ducts include bile duct adenoma, biliary adenofibroma, and mucinous cystic neoplasm, whereas those of the gallbladder and extrahepatic bile ducts include biliary intraepithelial neoplasia, intraductal papillary neoplasm of the bile ducts, intraductal tubulopapillary neoplasm of the bile ducts, intraductal oncocytic papillary neoplasm of the bile ducts, and mass-forming intracholecystic neoplasm. Despite these advances, their histological and molecular heterogeneity continues to pose significant diagnostic challenges, particularly in distinguishing them from malignant biliary tumors on limited biopsy specimens and in recognizing early invasive lesions. This review summarizes the clinicopathological and molecular features of benign biliary tumors and precursor neoplasms, emphasizing differential diagnosis and key updates introduced in WHO DST6.
1. Introduction
The sixth edition of the World Health Organization (WHO) Classification of Digestive System Tumours (WHO DST6), published online in 2026, introduced substantial revisions to the classification of benign biliary tumors and precursor neoplasms [1,2]. According to WHO DST6, benign biliary tumors and precursor neoplasms of the liver and intrahepatic bile ducts include bile duct adenoma (BDA), biliary adenofibroma (BAF), and mucinous cystic neoplasm (MCN), whereas those of the gallbladder and extrahepatic bile ducts include biliary intraepithelial neoplasia (BilIN), intraductal papillary neoplasm of the bile ducts (IPNB), intraductal tubulopapillary neoplasm (ITPN) of the bile ducts, intraductal oncocytic papillary neoplasm (IOPN) of the bile ducts, and mass-forming intracholecystic neoplasm (ICN). The evolution of the WHO classification for these entities is summarized in Table 1.
Table 1.
Evolution of the World Health Organization (WHO) classification of benign biliary tumors and precursor neoplasms.
Despite the rarity of benign biliary tumors and precursor neoplasms, marked geographic variation in incidence, variable malignant potential, and pathogenetic overlap with pancreatic precursor neoplasms underscore their clinical significance [3,4,5]. Noninvasive epithelial neoplasms of the biliary tract and pancreas share common differentiation pathways and recurrent genetic alterations, supporting a unified model of stepwise pancreaticobiliary tumorigenesis [6,7,8].
Despite advances in molecular characterization and classification systems, these lesions remain diagnostically challenging. Substantial histological overlap among reactive, benign, preinvasive, and early invasive lesions—compounded by molecular heterogeneity—further complicates diagnostic interpretation. Although WHO DST6 offers an integrated clinicopathological and molecular framework, its application in routine practice necessitates a systematic approach.
This review summarizes benign biliary tumors and precursor neoplasms according to WHO DST6, emphasizing diagnostic criteria, molecular pathogenesis, and differential diagnosis. Lesions of the liver and intrahepatic bile ducts are addressed first, followed by those of the gallbladder and extrahepatic bile ducts, to provide a practical, diagnostically oriented framework for pathologists and clinicians.
A literature search of PubMed and Google Scholar was conducted for articles published through April 2026 using keywords including “biliary precursor neoplasms,” “IPNB,” and other entities recognized in the WHO DST6. Literature selection prioritized high-quality original studies, expert consensus statements, and molecular landscape investigations to provide a comprehensive overview of the current evidence.
2. Benign Biliary Tumors and Precursor Neoplasms in the Liver and Intrahepatic Bile Ducts
2.1. Bile Duct Adenoma
2.1.1. Clinical Features
BDA is a benign nodular lesion characterized by the proliferation of small bile ducts. It is detected in approximately 0.6% of autopsy cases [9] and 2.4% of liver resection specimens [10]. BDA typically presents as a solitary subcapsular nodule (approximately 90% of cases), although it may occur anywhere in the liver. It predominantly affects adults and shows no sex predilection. On imaging, BDA typically presents as a small, well-circumscribed, hypovascular nodule in the subcapsular region of the liver. The pathogenesis of BDA remains uncertain. The proposed mechanisms include reactive changes secondary to focal injury [11] and an origin from peribiliary glands [12]. Atypical features, including larger size and microcystic changes, have been reported and may raise concern for malignant transformation [13,14].
2.1.2. Molecular Features
BRAF p.V600E mutations have been identified in approximately 53% of BDAs, supporting a neoplastic rather than purely reactive nature in a subset of cases [15,16].
2.1.3. Pathological Features
Grossly, BDA typically presents as a small (<10 mm), white, firm, well-circumscribed, unencapsulated nodule that is usually solitary, although multiple nodules may occur. Histologically, it is characterized by a disordered proliferation of uniform small tubules embedded within a fibrous stroma, without infiltrative borders (Figure 1). The tubules are lined by bland cuboidal epithelial cells resembling bile ductules. Entrapped portal tracts are frequently present. The stroma commonly shows collagenization and chronic inflammatory infiltrates. Immunohistochemically, ductal cells express cytokeratin 7 (CK7) and CK19. Positivity for MUC5AC and MUC6 is observed in approximately 80–90% of cases [17]. Morphological variants include mucin production, collagenized stroma, and clear cell or oncocytic features [18,19]. The oncocytic variant is characterized by abundant eosinophilic cytoplasm and centrally located round nuclei.
Figure 1.
Bile duct adenoma. (a) A well-circumscribed, unencapsulated lesion is present (hematoxylin and eosin stain, ×1). (b) Uniform tubules lined by a single layer of cuboidal epithelial cells are embedded in hyalinized fibrous stroma, without cytological atypia or mitoses (hematoxylin and eosin stain, ×200). All images are representative gross and histopathological findings selected from the author’s institutional archives for illustrative purposes only. No new data analysis or previously unpublished data are included.
2.1.4. Differential Diagnosis
Differential diagnoses include ductular reaction (DR), von Meyenburg complex (VMC; biliary microhamartoma), and adenocarcinoma, including primary intrahepatic cholangiocarcinoma (iCCA) and metastatic tumors. DR is typically ill-defined and non-nodular. However, in cirrhosis, it may replace hepatocytes in areas of parenchymal extinction, resulting in a vaguely nodular lesion. VMCs are typically smaller than BDAs (usually <5 mm) and are characterized by irregular, angulated ducts within abundant fibrous stroma, often containing intraluminal bile. In contrast, BDA typically lacks cystic change and intraluminal bile. Small-duct type intrahepatic cholangiocarcinoma (SD-iCCA), particularly the cholangiolocellular subtype, may closely mimic BDA by demonstrating well-differentiated small ductular structures with only mild cytologic atypia. However, SD-iCCA can be distinguished from BDA by its larger size, more complex architecture, and invasive growth. Immunohistochemistry (IHC) for Ki-67, p53, EZH2, and p16 may be diagnostically useful, particularly in challenging cases [20,21]. BDAs demonstrate a low Ki-67 index (typically <10%) and lack strong p53 expression. Although EZH2 is expressed in carcinomas, it is typically absent in BDAs. p16 expression is typically retained in BDAs, whereas loss of expression is frequently observed in carcinomas. BDAs may also demonstrate C-reactive protein expression and albumin in situ hybridization (ISH) positivity [22].
2.1.5. Key Updates in the 6th WHO Classification
In WHO DST6, BDA has undergone conceptual refinement: the term “peribiliary gland hamartoma” is no longer recommended, and accumulating evidence supports a neoplastic nature in a subset of cases, particularly those harboring BRAF p.V600E mutations. Furthermore, the recognized anatomical spectrum has been expanded to encompass lesions beyond the hepatic subcapsular region.
2.2. Biliary Adenofibroma
2.2.1. Clinical Features
BAF is a rare benign intrahepatic epithelial neoplasm with a solid and microcystic architecture, composed of variably dilated tubules lined by nonmucinous biliary epithelium within a fibrotic stroma. BAF is extremely rare, with published data limited to case reports and small series [23,24,25,26]. Affected patients range in age from 23 to 83 years (median, 57 years), with a slight female predominance. BAF has no predilection for a specific hepatic location. Patients may present with abdominal pain; however, incidental detection is common. On imaging, BAF appears as a well-circumscribed mass with a sponge-like appearance, reflecting mixed solid and microcystic components. Malignant transformation has been reported in approximately 50% of cases [24,27].
2.2.2. Molecular Features
Recurrent hotspot mutations are absent in BAF; however, the presence of multiple clonal cytogenetic alterations supports a neoplastic nature. CCND1 and ERBB2 amplifications have been identified and may be associated with biological aggressiveness. CDKN2A (p16) and/or NRAS mutations have been reported in rare cases, particularly those associated with malignant transformation [28,29].
2.2.3. Pathological Features
Grossly, BAF presents as a solitary, well-circumscribed but unencapsulated, round to oval mass (17–160 mm). On cut section, the tumor shows mixed solid and microcystic (sponge-like) areas, with occasional macrocysts (>10 mm). Histologically, it is composed of acini, tubules, and cysts embedded within an abundant fibrotic stroma. The tubules are often dilated and branched, and the cysts vary in size, occasionally showing intraluminal polypoid projections. The lining epithelium is single-layered and nonmucinous, consisting of cuboidal to low columnar cells, with amphophilic cytoplasm and bland nuclei; focal epithelial flattening and apocrine snouts may be present. The stroma is collagenous and relatively hypocellular, containing bland spindle-shaped myofibroblasts with patchy mononuclear inflammatory infiltrates. The epithelium demonstrates a biliary immunophenotype (positivity for EMA, CK7, CK19, and CA19-9), and the Ki-67 proliferation index is low (<10% in the epithelium; <1% in the stroma). Premalignant dysplasia is observed in approximately 50% of cases and is characterized by nuclear atypia (elongation, hyperchromasia, and pseudostratification) [24] and increased architectural complexity (intracystic, papillary, and cribriform growth patterns) [30,31]. Carcinoma arising from BAF most commonly resembles conventional adenocarcinoma, consistent with SD-iCCA [32,33]; rare cases of microcystic-cribriform carcinoma have also been reported [34].
2.2.4. Differential Diagnosis
Differential diagnoses include VMC and the tubulocystic variant of SD-iCCA. Small BAFs may overlap with large VMCs. Smaller lesions (<1 cm) are typically consistent with VMC, whereas lesions > 2 cm favor BAF; the presence of prominent micro- or macrocysts further supports a diagnosis of BAF. Tubulocystic SD-iCCA may exhibit BAF-like areas [35]. Shared chromatin-remodeling gene alterations (e.g., ARID1A, BAP1, IDH2, and PBRM1) or an FGFR2::MCU fusion gene in both adenocarcinoma and BAF-like components support the neoplastic and potentially malignant nature of the BAF-like component [35,36]. The presence of a conventional SD-iCCA component or cytologic atypia favors tubulocystic iCCA, whereas BAF is typically well-circumscribed, with hypocellular fibrotic stroma and bland cytology.
2.2.5. Key Updates in the 6th WHO Classification
In WHO DST6, BAF is more precisely defined as a benign intrahepatic epithelial neoplasm with a malignant transformation rate of approximately 50%. Accumulating molecular data, including NRAS mutations alongside CDKN2A alterations, further expands the spectrum of genetic changes associated with malignant transformation. Furthermore, the morphological overlap with tubulocystic SD-iCCA highlights the importance of thorough histological assessment to exclude invasive carcinoma.
2.3. Mucinous Cystic Neoplasm
2.3.1. Clinical Features
Mucinous cystic neoplasm (MCN) is a rare, cyst-forming epithelial neoplasm characterized by mucin-producing cuboidal to columnar epithelium overlying ovarian-type stroma, with no communication with the bile ducts. Its incidence is approximately 1 per 20,000–100,000 person-years [37,38], and it accounts for approximately 10% of all hepatic cysts [39]. MCN occurs almost exclusively in women, and the presence of ovarian-type stroma supports a hormonal influence [37]. The mean patient age is 52 years [39], with patients harboring invasive carcinoma presenting at an older age (mean, 61 years) than those with noninvasive MCN (mean, 50.4 years) [40]. Tumors are predominantly intrahepatic [37,40,41] and typically solitary, most commonly arising in the left lobe (particularly segment IV). Rare cases arising in the gallbladder have been reported [42,43]. Clinically, patients usually present with abdominal pain or distension. Elevated CA19-9 and CEA levels in serum or cyst fluid may help distinguish MCN from non-neoplastic cysts [44,45]. On imaging, MCN characteristically appears as a multilocular cystic mass with internal septations; wall thickening, irregular septa, or papillary projections should raise suspicion for associated invasive carcinoma [46,47]. Prognosis following complete surgical resection is excellent [38,48]. Associated invasive carcinoma is uncommon (approximately 6%), and although it confers a worse prognosis than noninvasive MCN, outcomes remain more favorable than those of conventional iCCA [40,48].
2.3.2. Molecular Features
KRAS mutations are identified in approximately 20% of MCNs, whereas GNAS, RNF43, and PIK3CA are typically wild-type [40,41,49]. KRAS mutations are uncommon in low-grade dysplasia (approximately 5%) but more frequent in high-grade dysplasia, supporting their role in neoplastic progression. KRAS-mutated MCNs more often exhibit multilocular cystic morphology and increased expression of MUC1, MUC2, and MUC5AC compared with KRAS-wild-type tumors [41]. Progressive telomere shortening has been observed during progression to invasive carcinoma [50]. Primordial germ cells may represent a shared cell of origin for pancreatic MCN and mucinous ovarian tumors [51], a concept potentially applicable to hepatobiliary MCN given their morphological and molecular similarities.
2.3.3. Pathological Features
Grossly, MCNs are well-circumscribed, multilocular cystic lesions (50–290 mm; mean, 110 mm) [38,40,41,52], typically separate from the biliary tree. The inner surface is smooth or trabeculated, occasionally with papillary projections, and the cysts contain mucinous, clear, or hemorrhagic fluid. Associated invasive carcinoma may appear as a solid, gray-white mural nodule or mass. Histologically, the cysts are lined by columnar, cuboidal, or flattened epithelial cells with mucinous or pale eosinophilic cytoplasm and basally oriented nuclei, occasionally forming papillary structures (Figure 2a). Approximately 50% show nonmucinous biliary-type epithelium, and scattered neuroendocrine cells are identified in approximately 50% of cases [40,53]. The ovarian-type stroma is hypercellular and often rimmed by fibrous tissue [40,41], with focal luteinization or hyalinization in some cases. Degenerative changes, including hemorrhage, calcification, and necrosis, and associated inflammation, are common [40]. Immunohistochemically, the epithelial cells are positive for CK7, CK8, CK18, CK19, EMA, CEA, and MUC5AC [40] and may show gastric or intestinal differentiation or squamous metaplasia. Stromal cells are positive for ER, PR, and α-inhibin (Figure 2b) [40,42]. Most MCNs exhibit low-grade dysplasia; high-grade dysplasia, characterized by marked architectural atypia and increased mitotic activity, is uncommon [40]. Invasive carcinoma occurs in approximately 6% of cases, typically as tubular or tubulopapillary adenocarcinoma with desmoplastic stroma, resembling large-duct type intrahepatic cholangiocarcinoma (LD-iCCA) (Figure 3) [40,41].
Figure 2.
Mucinous cystic neoplasm with low-grade intraepithelial neoplasia. (a) The cyst is lined by columnar epithelial cells with mucinous cytoplasm, with underlying ovarian-type spindle cell stroma (hematoxylin and eosin stain, ×100). (b) The ovarian-type stromal cells are positive for progesterone receptor (PR), while the overlying epithelium is negative for PR (immunohistochemical stain, ×100).
Figure 3.
Mucinous cystic neoplasm with associated invasive adenocarcinoma. (a) A multiloculated cystic tumor is present in the left hepatic lobe, with internal septations containing mucinous and hemorrhagic material. (b) The tumor is lined by low-grade mucinous epithelium with underlying ovarian-type stroma (hematoxylin and eosin stain, ×100). (c) A transition from low-grade to high-grade dysplasia with marked cytological atypia is present (hematoxylin and eosin stain, ×100). (d) An associated invasive adenocarcinoma component is identified within the mucinous cystic neoplasm (hematoxylin and eosin stain, ×100).
2.3.4. Differential Diagnosis
Differential diagnoses include solitary bile duct cyst (simple cyst), ciliated foregut cyst, endometriotic cyst, and IPNB. Solitary bile duct cysts are typically unilocular and lack ovarian-type stroma. Ciliated foregut cysts are distinguished by their ciliated epithelium and lack ovarian-type stroma. Endometriotic cysts contain endometrial glands and stroma, and ER and PR are positive in both epithelium and stromal cells of endometriotic cysts, whereas in MCNs, ER and PR expression is restricted to stromal cells [54]. Unlike MCNs, IPNBs communicate with the bile ducts and lack ovarian-type stroma. The presence of ovarian-type stroma is a defining diagnostic criterion for MCN; its absence precludes the diagnosis.
2.3.5. Key Updates in the 6th WHO Classification
In WHO DST6, the definition of MCN has been refined as a noninvasive cyst-forming epithelial neoplasm with ovarian-type stroma and no communication with the bile ducts. The grading system has been simplified to a two-tiered scheme (low- and high-grade dysplasia), enhancing diagnostic reproducibility. Molecularly, KRAS mutations are recognized as progression-associated events that occur more frequently in high-grade dysplasia. The absence of GNAS mutations and the presence of progressive telomere shortening support a stepwise precursor-to-carcinoma progression model.
Table 2 summarizes the clinicopathological and molecular features of benign biliary tumors and precursor neoplasms in the liver and intrahepatic bile ducts.
Table 2.
Clinicopathological and molecular features of benign biliary tumors and precursor neoplasms in the liver and intrahepatic bile ducts.
3. Benign Biliary Tumors and Precursor Neoplasms in the Gallbladder and Extrahepatic Bile Ducts
3.1. Biliary Intraepithelial Neoplasia
3.1.1. Clinical Features
BilIN is a microscopic, noninvasive flat or (micro)papillary epithelial neoplasm involving the large bile ducts and gallbladder. It may involve the entire extrahepatic biliary tree and the large intrahepatic bile ducts, while generally sparing the small terminal intrahepatic bile ducts. BilIN is usually detected incidentally in resected specimens. BilIN is radiologically occult as a microscopic lesion, although subtle mucosal thickening or irregularity may be detected on high-resolution cholangiography. It is identified in the surrounding mucosa of up to 80% of invasive gallbladder carcinomas [55,56]. In endemic regions, low-grade BilIN is observed in up to 15% of gallbladders with cholelithiasis, whereas high-grade BilIN occurs in 1.5–3.5% of cases [57]. The prevalence of high-grade BilIN parallels that of invasive biliary carcinoma [57] and shows marked geographic variation, occurring in up to 5% of cases in East Asia compared with <0.1% in North America [57,58]. BilIN is associated with hepatolithiasis, cholelithiasis, primary sclerosing cholangitis (PSC) [59,60], choledochal cyst [61], anomalous union of the pancreaticobiliary ducts (AUPBD) [62], and parasitic infections (e.g., Opisthorchis viverrini and Clonorchis sinensis) [63].
3.1.2. Molecular Features
Chronic inflammation plays a central role in the pathogenesis of BilIN [64]. In the gallbladder, persistent inflammation induces oxidative stress, which causes DNA damage and genomic instability. The effects of this are exacerbated by defects in DNA repair genes (e.g., ATM and BRCA2) and by epigenetic alterations, including the hypermethylation of tumor suppressor gene promoters such as FHIT, APC, CDKN2A, CDH1, RB1, TP53, and DCC. Genomic studies have identified recurrent mutations in several genes (e.g., CTNNB1, ARID2, TP53, ERBB3, NFE2L2, PIK3CA, SMARCA4, KRAS, and SMAD4) [65,66], with CTNNB1 mutations implicated in the progression to invasive carcinoma [65]. In the large bile ducts, KRAS mutations are often early events, present in 30–40% of low-grade BilIN, whereas TP53 alterations occur later in tumor progression [67,68,69].
3.1.3. Pathological Features
Grossly, BilIN lesions are typically inapparent, although subtle mucosal thickening or textural changes may be present. Histologically, BilIN is graded as low- or high-grade based on cytoarchitectural atypia [70]. This two-tiered system replaces the previous BilIN-1/2 (low-grade) and BilIN-3 (high-grade) classification [70,71]. Low-grade BilIN shows mild cytological atypia, predominantly flat growth, nuclear pseudostratification, increased nuclear-to-cytoplasmic ratio, hyperchromasia, and preserved basal polarity (Figure 4a). High-grade BilIN exhibits complex architecture (micropapillary or tall papillary), loss of polarity, marked nuclear atypia, and frequent mitoses (Figure 4b) [72]. Low-grade BilIN is usually focal and rarely associated with invasive carcinoma, whereas high-grade BilIN is often extensive and frequently associated with invasive carcinoma [55,73,74]. Phenotypes (biliary, intestinal, gastric) lack clear clinical significance and do not necessarily correlate with invasive components [75]. The epithelium adjacent to BilIN lesions is often inflamed and reactive, frequently showing intestinal or foveolar-type gastric metaplasia [66,76,77,78].
Figure 4.
Biliary intraepithelial neoplasia (BilIN). (a) Low-grade BilIN shows nuclear pseudostratification with an increased nuclear-to-cytoplasmic (N:C) ratio and nuclear hyperchromasia (hematoxylin and eosin stain, ×200). (b) High-grade BilIN shows irregular nuclei, a high N:C ratio, and loss of polarity. Epithelial budding is present (hematoxylin and eosin stain, ×200).
3.1.4. Differential Diagnosis
Differential diagnoses include reactive epithelial atypia (REA) and invasive adenocarcinoma. The distinction between BilIN and REA can be challenging. REA typically involves both the surface epithelium and intramural glands, characterized by attenuated basophilic cells, intercellular clefts, occasional nuclear molding, fine chromatin, small to conspicuous nucleoli, and brisk mitotic activity. A gradual transition from normal to atypical epithelium favors REA rather than BilIN. Immunohistochemically, p53 overexpression supports the diagnosis of BilIN [79,80,81]. MUC5AC and S100P expression may increase with higher-grade dysplasia [82,83,84,85]; however, their variable expression limits diagnostic utility. High-grade BilIN in the gallbladder may arise from or extend into Rokitansky–Aschoff sinuses, mimicking invasive adenocarcinoma [86,87]. In this setting, the absence of a desmoplastic stromal reaction and irregular stromal invasion, along with confinement of the lesion to preexisting sinus structures, favors BilIN over invasive adenocarcinoma.
3.1.5. Key Updates in the 6th WHO Classification
In WHO DST6, the etiological spectrum has been expanded to include parasitic infections. The updated classification emphasizes chronic inflammation and incorporates DNA repair defects, epigenetic alterations, and recurrent somatic mutations into the molecular framework of BilIN. Notably, CTNNB1 mutations have been implicated as potential drivers of progression to invasive carcinoma.
3.2. Intraductal Papillary Neoplasm of the Bile Ducts
3.2.1. Clinical Features
IPNB is a grossly visible, noninvasive epithelial neoplasm of the large intrahepatic and extrahepatic bile ducts, characterized by intraluminal papillary or tubular proliferations of mucin-producing columnar cells. Its prevalence shows marked geographic variation, accounting for 10–38% of bile duct tumors in East Asia but only 7–11% in Western countries [88,89,90,91]. Patients are typically aged 42–80 years, with a slight male predominance [92,93]. The anatomical distribution varies between intrahepatic and extrahepatic sites [93,94]. IPNB appears as an intraluminal polypoid or papillary mass associated with bile duct dilatation on cross-sectional imaging. On cholangiography, IPNB typically presents as intraluminal filling defects, although lesions may occasionally be occult [95,96]. Clinically, patients typically present with recurrent abdominal pain, jaundice, and cholangitis [4,93,96,97]. The etiology is not fully defined; however, risk factors include PSC [98], hepatolithiasis, and liver fluke infection (Clonorchis sinensis and Opisthorchis viverrini)—particularly in East Asian populations [99,100,101]—and pancreaticobiliary maljunction (PBM) [102,103]. IPNB progresses from low-grade to high-grade dysplasia and may evolve into invasive carcinoma [6,93,100]. IPNB-associated invasive carcinoma is associated with better survival than conventional CCA.
3.2.2. Molecular Features
IPNB develops through the stepwise accumulation of somatic alterations, including KRAS mutations, p16 loss, and inactivating TP53 mutations [6,104,105]. Molecular heterogeneity correlates with histological subtypes. GNAS mutations are identified in a subset of IPNBs, predominantly in the intestinal subtype characterized by villous architecture and mucin hypersecretion [105,106,107,108]. RNF43 mutations are also enriched in the intestinal subtype [106].
3.2.3. Pathological Features
Grossly, IPNBs present as intraluminal polypoid or papillary masses within dilated bile ducts. These dilated ducts may be cystic, cylindrical, or fusiform (mean diameter, 41 ± 22 mm), with papillary projections measuring 5–20 mm [4,105,109]. Lesions may be solitary or multifocal and are often associated with mucin hypersecretion [4,110]. Progression to invasive carcinoma may occur; invasion is usually limited but can occasionally be nodular or mass-forming. Histologically, IPNBs show papillary or villous structures lined by neoplastic epithelium and supported by delicate fibrovascular cores, sometimes with tubular or glandular components [6,105]. IPNBs are graded as low-grade or high-grade dysplasia, with high-grade lesions more frequent in extrahepatic sites [94,105]. IPNBs are subclassified into gastric (Figure 5), intestinal (Figure 6), and pancreaticobiliary (Figure 7) types based on morphology and immunophenotype, with frequent mixed differentiation [105,111,112]. Immunohistochemically, MUC1 expression supports pancreaticobiliary differentiation, MUC2 and CDX2 expression supports intestinal differentiation, and MUC5AC and MUC6 support gastric differentiation [105]. Intestinal and gastric subtypes predominate in Asia, whereas the pancreaticobiliary subtype is more common in Western populations [105]. An associated invasive carcinoma is present in approximately 40–80% of IPNBs at the time of resection, most commonly tubular adenocarcinoma and less frequently colloid carcinoma [6,100,105]. Association with SD-iCCA is rare [105].
Figure 5.
Intraductal papillary neoplasm of the bile duct with low-grade intraepithelial neoplasia. (a) A multinodular papillary lesion is present in the extrahepatic biliary tract, including the common hepatic duct, common bile duct, cystic duct, and gallbladder neck. (b) The tumor shows a papillary growth pattern lined by tall columnar cells with abundant pale mucin, consistent with gastric foveolar-type differentiation (hematoxylin and eosin stain, ×100).
Figure 6.
Intraductal papillary neoplasm of the bile duct with high-grade intraepithelial neoplasia. (a) A brown solid tumor fills the lumen of the intrahepatic bile duct and is associated with multiple pigmented stones. (b) The tumor shows intestinal-type differentiation with a papillary growth pattern characterized by pseudostratified columnar cells with elongated nuclei and marked cytological atypia (hematoxylin and eosin stain, ×200).
Figure 7.
Intraductal papillary neoplasm of the bile duct with associated invasive adenocarcinoma. (a) A multinodular lesion is present in the lumen of the left intrahepatic duct. (b) The tumor shows a papillary growth pattern lined by biliary-type cuboidal epithelium with low-grade dysplasia (hematoxylin and eosin stain, ×100). (c) A transition from low-grade to high-grade dysplasia with marked cytological atypia is present (hematoxylin and eosin stain, ×200). (d) An invasive adenocarcinoma component with glandular architecture and desmoplastic stroma is identified (hematoxylin and eosin stain, ×200).
IPNB is additionally divided into two types with distinct clinicopathological features [4,99,113]. Type 1 occurs predominantly in intrahepatic ducts, shows cystic or cylindrical dilatation with frequent mucin hypersecretion, and displays a relatively regular papillary architecture with fine fibrovascular cores. It is generally of the gastric or intestinal subtype and is typically high-grade, often with focal low-grade areas. Stromal invasion, when present, is limited. It resembles pancreatic intraductal papillary mucinous neoplasm and generally has a favorable prognosis. Type 2 arises predominantly in extrahepatic ducts, exhibits complex architecture with cribriform or solid areas, and shows minimal mucin production. It is typically of the intestinal or pancreaticobiliary subtype, is almost always high-grade (occasionally with focal low-grade areas), and frequently shows stromal invasion. It behaves more aggressively and is associated with a worse prognosis [92,94,114,115].
3.2.4. Differential Diagnosis
Differential diagnoses include micropapillary BilIN, ITPN, and intraductal polypoid metastases [116,117,118]. Micropapillary BilIN is a microscopic lesion (<3 mm) in the large intrahepatic bile ducts and is often intermixed with flat or pseudopapillary BilIN. ITPN forms a cast-like intraluminal lesion composed of densely packed tubular glands with high-grade architectural and cytological atypia. Mucin production is absent, and MUC5AC expression is typically negative. Intraductal polypoid metastases, most commonly originating from colorectal carcinoma, lack a precursor papillary component and show an abrupt transition to invasive carcinoma.
3.2.5. Key Updates in the 6th WHO Classification
In WHO DST6, IPNB is retained as a grossly visible, noninvasive precursor neoplasm of the large bile ducts. The updated classification formally recognizes the pancreaticobiliary, intestinal, and gastric subtypes, whereas ITPN and IOPN are distinct entities. The type 1/type 2 framework is further clarified: type 2 is characterized by a more complex architecture, invariably high-grade dysplasia, and a stronger association with invasive carcinoma. Molecularly, IPNB pathogenesis follows a stepwise model involving KRAS mutations, p16 loss, and TP53 inactivation, with GNAS and RNF43 mutations being enriched, particularly in the intestinal subtype.
3.3. Intraductal Tubulopapillary Neoplasm of the Bile Ducts
3.3.1. Clinical Features
ITPN of the bile ducts is a rare, noninvasive intraductal epithelial neoplasm characterized by tubular structures with focal papillary areas, predominantly high-grade dysplasia, and minimal mucin production. It accounts for approximately 15% of intraductal bile duct neoplasms [93] and shows a female predominance (male-to-female ratio, approximately 1:2), typically occurring in the sixth decade (range, 38–78 years; median, 63 years) [117,119]. Approximately 70% arise in the intrahepatic bile ducts, followed by perihilar (20%) and extrahepatic (10%) locations [117]. Clinically, ITPN may be detected incidentally or present with nonspecific symptoms such as abdominal pain and anorexia, occasionally with weight loss or jaundice [117]. Serum CA19-9 and CEA levels may be elevated. Radiological findings include intraductal filling defects, bile duct dilatation, or a solid mass, occasionally cystic in intrahepatic cases [119,120]. Although the etiology remains unclear, associations with hepatobiliary diseases such as calculi, cirrhosis, PSC, and chronic hepatitis B have been reported [105,121]. Approximately 80% of cases progress to invasive carcinoma, most commonly (approximately 60%) as conventional tubular CCA of small- or large-duct type [105,117]. Despite the high rate of progression to invasive carcinoma, prognosis after resection is excellent, with 1- and 3–5-year survival rates of approximately 100% and 90%, respectively [117]. Even with invasive carcinoma, outcomes remain favorable (5-year survival of approximately 75%), being significantly better than those of conventional CCA [105]. The discrepancy between the high frequency of invasion and the unexpectedly favorable patient outcomes may be attributed to early detection prompted by biliary obstruction or ductal dilatation and to the relatively limited extent of invasive growth in many cases.
3.3.2. Molecular Features
ITPN lacks hotspot mutations in common driver genes of pancreaticobiliary carcinogenesis, such as KRAS, GNAS, and IDH1/2, with only occasional CDKN2A alterations reported [93,105,117,122,123]. Instead, low-prevalence alterations in cell cycle regulation, chromatin remodeling (e.g., the SWI/SNF complex, BAP1, and KMT2C), and receptor tyrosine kinase pathways (e.g., FGFR) support a KRAS-independent tumorigenic mechanism [93,105,117,123]. Shared chromatin-remodeling gene alterations with CCA suggest partial molecular overlap and a potential biological continuum. Epigenetically, ITPN is further distinguished from IPNB: ITPN has been proposed to arise from MUC6-positive peribiliary glands or cysts [105], whereas IPNB is thought to originate from MUC5AC-positive surface biliary epithelium [120]. MUC5AC-negative biliary ITPNs are genetically distinct from pancreatic ITPNs and IPNBs and may represent a biologically distinct entity from MUC5AC-positive tubular neoplasms, despite their morphological similarities [124].
3.3.3. Pathological Features
Grossly, ITPNs present as solid, whitish-to-tan nodular masses within dilated bile ducts, often with punctate or geographic necrosis [119,120]. Cyst formation and overt mucin production are uncommon. The mean tumor size is 50 mm (range, 6–150 mm). When invasion occurs, it typically presents as an irregular, firm, whitish mass (Figure 8a). Histologically, biliary ITPNs closely resemble pancreatic ITPNs and show a relatively homogeneous, multinodular architecture composed of tightly packed tubular glands with frequent cribriform formation [93,119,120]. Papillary structures generally comprise <30% of the tumor, and less differentiated solid components may coexist. The tumor cells are cuboidal to columnar, with amphophilic cytoplasm and enlarged nuclei, often with conspicuous nucleoli, consistent with high-grade dysplasia. Nuclear grooves may be present. Mitotic activity is readily identified; additional features may include focal clear or oncocytic changes and occasional intraluminal eosinophilic (colloid-like) secretions, whereas intracytoplasmic mucin is typically absent. Necrosis is common (approximately 85%), usually focal or comedo-like [93,119,120,124]. Invasive carcinoma, when present, most commonly consists of conventional tubular adenocarcinoma of small-duct or large-duct type (Figure 8b). Approximately 25% exhibit an intraductal-like growth pattern with extensive comedonecrosis, and a distinct tubulocystic pattern—characterized by dilated tubular structures lined by bland cells—has been reported [117]. Immunohistochemically, tumor cells are consistently positive for pancytokeratins, CK7, and CK19. MUC1 is expressed in approximately 80% of cases, and MUC6 expression varies (30–100%) [93,117,119], whereas MUC2 and MUC5AC are typically negative [93,117,119].
Figure 8.
Intraductal tubulopapillary neoplasm of the bile ducts with associated invasive adenocarcinoma. (a) A gray-white solid tumor fills the lumen of the intrahepatic bile duct, invades the bile duct wall, and extends into the liver parenchyma. (b) The tumor shows a tubulopapillary growth pattern composed of cuboidal cells, with an associated invasive adenocarcinoma component in the lower field (hematoxylin and eosin stain, ×100).
3.3.4. Differential Diagnosis
Differential diagnoses include BilIN, IPNB, and iCCA. BilIN is distinguished by its flat or micropapillary growth pattern, lack of grossly visible lesions, and predominantly biliary-type morphology. Mucin production, MUC5AC expression, and a heterogeneous spectrum of dysplasia favor IPNB over ITPN [124]. Mass-forming iCCA may extend into large bile ducts and exhibit intraductal tubular growth mimicking ITPN; however, the dominant tumor mass typically resides within the hepatic parenchyma, a feature uncharacteristic of ITPN.
3.3.5. Key Updates in the 6th WHO Classification
Unlike the 5th edition, which described ITPN only as a morphological pattern within IPNB resembling pancreatic ITPN, WHO DST6 formally recognizes biliary ITPN as a distinct entity with well-defined clinicopathological criteria. The updated classification delineates its epidemiology and clinicopathological features, emphasizes its KRAS-independent molecular profile characterized by chromatin-remodeling gene alterations, and establishes diagnostic criteria, staging, and prognostic implications.
3.4. Intraductal Oncocytic Papillary Neoplasm of the Bile Ducts
3.4.1. Clinical Features
IOPN of the bile ducts is a rare, intraductal epithelial neoplasm characterized by exophytic papillary or nodular proliferation of oncocytic cells with abundant granular eosinophilic cytoplasm. It predominantly affects middle-aged to older adults (range, 38–81 years; mean, 60 years) and shows a slight female predominance [125,126,127,128]. Approximately 70% arise in the intrahepatic bile ducts, whereas the remainder involve the extrahepatic ducts (15%) or both intra- and extrahepatic sites (15%) [127]. IOPN accounts for approximately 9–15% of grossly visible intraductal biliary precursor neoplasms [93,126,127]. Most lesions are incidentally detected, although some patients present with abdominal mass or jaundice [128,129,130]. On imaging, IOPN typically appears as an intraductal papillary or nodular mass within dilated bile ducts and usually lacks diffuse mucin-related ductal dilatation. Associated invasive carcinoma is identified in approximately 30–40% of cases [127,128]. Nevertheless, the overall prognosis is more favorable than that of IPNB-associated invasive carcinoma [127].
3.4.2. Molecular Features
The pathogenesis of biliary IOPN parallels that of pancreatic IOPN and exhibits a distinct molecular profile [131,132,133]. Unlike IPNB, conventional driver mutations (e.g., KRAS, BRAF, GNAS, RNF43, PIK3CA, and SMAD4) are typically absent in IOPN [6,93,134,135]. Instead, IOPNs harbor recurrent gene fusions involving PRKACA or PRKACB—including ATP1B1::PRKACB, ATP1B1::PRKACA, and DNAJB1::PRKACA—resulting from characteristic chromosomal rearrangements, such as t(1;1)(p31;q24), t(1;19)(q24;p13), and focal chromosome 19 deletion [93,134,136]. These fusions are retained in IOPN-associated invasive carcinomas, supporting their role as early driver alterations [134]. Mechanistically, these fusions activate protein kinase A signaling, leading to mitochondrial hyperplasia and the oncocytic phenotype [137].
3.4.3. Pathological Features
IOPNs closely resemble pancreatic IOPNs both macroscopically and microscopically [128,133,138,139]. They typically present as large (mean, 53 mm) intraductal masses with friable papillary projections or solid nodules within dilated bile ducts, generally with minimal mucin production (Figure 9a) [112,127,128]. Histologically, biliary IOPNs form complex, arborizing papillae with delicate fibrovascular stroma. The papillae are lined by cuboidal to columnar oncocytic cells with abundant granular eosinophilic cytoplasm, large nuclei, and prominent nucleoli (Figure 9b) [93,140]. They may exhibit cribriform architecture with intraepithelial lumina, scattered goblet cells, and occasional solid growth resulting from papillary fusion. In some cases, oncocytic tumor cells are admixed with gastric foveolar-like tall columnar epithelial cells with subnuclear oncocytic cytoplasm [135,141]. All cases show high-grade dysplasia with architectural complexity and nuclear atypia; inflammatory infiltrates, including lymphocytes and neutrophils, are common. Approximately 30–40% of IOPNs progress to invasive carcinoma, usually composed of small infiltrating tubules or solid nests of oncocytic cells [127,128]. Lymphovascular and perineural invasion, as well as lymph node metastasis, occur at frequencies comparable with those in IPNB-associated carcinoma [127]. Immunohistochemically, tumor cells diffusely express MUC5AC and MUC6 and show focal MUC1 positivity, whereas MUC2 expression is limited to goblet cells [6,93,130,135,142,143]. The mucin expression profiles are similar to those of pancreatic IOPNs [113]. Hepatocyte paraffin 1 (Hep Par-1) and KIT (CD117) are also frequently expressed [127,128].
Figure 9.
Intraductal oncocytic papillary neoplasm of the bile duct. (a) A brown-tan solid tumor fills the lumen of the intrahepatic bile duct. (b) The tumor is composed of cuboidal-to-columnar cells with round, uniform nuclei and abundant eosinophilic granular cytoplasm (hematoxylin and eosin stain, ×100).
3.4.4. Differential Diagnosis
Differential diagnoses include IPNB, particularly the pancreaticobiliary subtype, and well-differentiated neuroendocrine tumor (NET). IOPNs are distinguished from IPNBs by their complex cribriform architecture lined by oncocytic cells and diffuse MUC6 expression. Well-differentiated NETs should also be considered, particularly when oncocytic or hepatoid features are present [144,145]. In such cases, neuroendocrine markers (chromogranin A and synaptophysin) should be used alongside IOPN-associated markers (Hep Par-1 and KIT (CD117)) to exclude NET.
3.4.5. Key Updates in the 6th WHO Classification
WHO DST6 formally recognizes biliary IOPN as a distinct entity that shares similar pathogenetic and histopathological features with its pancreatic counterpart. This edition emphasizes its unique molecular profile, characterized by the absence of common driver mutations and the presence of recurrent PRKACA and PRKACB fusions.
3.5. Mass-Forming Intracholecystic Neoplasm
3.5.1. Clinical Features
Mass-forming ICNs are grossly visible, noninvasive polypoid or papillary neoplasms composed of dysplastic epithelium that projects into the gallbladder lumen. According to WHO DST6, mass-forming ICN is a broad category that is histologically subclassified into intracholecystic papillary neoplasm (ICPN) and intracholecystic tubular neoplasm (ICTN) based on their predominant architectural patterns. ICNs account for approximately 0.4% of cholecystectomy specimens; approximately 6% of gallbladder carcinomas arise within them [146]. ICNs predominantly affect adults (mean, 61 years) with a female predominance [146,147,148,149]. Approximately half of patients present with right upper quadrant pain, whereas the remainder are incidentally detected on imaging, often mimicking gallbladder carcinoma [146]. On imaging, ICPN is usually seen as a papillary or polypoid intraluminal mass, whereas ICTN may appear as a compact, sessile, or nodular intraluminal mass. Imaging features such as focal wall thickening, irregular margins, or adjacent hepatic invasion are suggestive of associated invasive carcinoma. ICNs are frequently associated with gallstones [146] and may arise in PSC or PBM [150]. Lesions associated with gallstones or chronic inflammatory conditions are thought to progress through the inflammation–injury–dysplasia–carcinoma sequence, whereas PBM-associated carcinogenesis is preceded by reflux cholecystopathy, defined as mucosal hyperplasia induced by pancreatic enzyme reflux [151]. The prognosis of noninvasive ICNs is excellent after cholecystectomy, whereas those with an invasive component show a 5-year survival of approximately 60% [146].
3.5.2. Molecular Features
ICTNs are primarily characterized by WNT signaling pathway alterations [152,153]. Unlike other pancreaticobiliary intraductal neoplasms, ICNs infrequently harbor canonical driver mutations such as KRAS and GNAS [148,154,155]; however, KRAS mutations occur more frequently in PBM-associated ICNs. TP53 alterations have been identified in ICPNs [156].
3.5.3. Pathological Features
Grossly, ICNs typically present as granular friable excrescences or exophytic polypoid or papillary mucosal lesions, with a median size of approximately 22 mm [146]. ICPNs are usually broad-based and often extensive, with multifocal lesions identified in approximately one-third of cases, whereas ICTNs are solitary, pedunculated polypoid masses with thin stalks [157]. ICNs arising within adenomyomas form well-demarcated mural nodules that often spare the overlying surface mucosa [158,159].
Intracholecystic Papillary Neoplasm
ICPNs are broad-based, exophytic lesions composed of neoplastic epithelial cells with predominantly papillary architecture and focal tubular components; they may extend into the Rokitansky–Aschoff sinuses, mimicking invasion. ICPNs show considerable morphologic heterogeneity, most commonly with biliary or gastric differentiation and, less frequently, intestinal differentiation, accompanied by corresponding mucin core protein expression patterns [146,149]. ICPNs are graded as low- or high-grade dysplasia based on the highest degree of cytoarchitectural atypia. High-grade dysplasia is characterized by increased architectural complexity, loss of polarity, and marked nuclear atypia (Figure 10) [146]. Rarely, ICPNs arise within adenomyomas as partly solid and cystic mural nodules; these lesions are usually low-grade, although invasive carcinoma has been reported in approximately 15% of cases [159]. More than half of ICPNs are associated with invasive carcinoma, particularly those with predominantly papillary architecture, biliary differentiation, or extensive high-grade dysplasia [146,149,160]. The invasive component is most often tubular adenocarcinoma; however, mucinous, adenosquamous, and neuroendocrine carcinomas may also occur [161,162].
Figure 10.
Intracholecystic papillary neoplasm with high-grade intraepithelial neoplasia. (a) A polypoid lesion is present in the fundus of the gallbladder. (b) The tumor shows a tubulopapillary growth pattern composed of biliary-type cuboidal cells with high-grade dysplasia (hematoxylin and eosin stain, ×100).
Intracholecystic Tubular Neoplasm
ICTNs, previously classified within the intracholecystic papillary–tubular neoplasm spectrum, demonstrate a complex tubular architecture composed of closely packed, back-to-back, acinar-like units lined by mucin-poor epithelial cells with round to ovoid nuclei—a feature that distinguishes them from tubular-predominant ICPNs (Figure 11) [146,150,157,163]. Morule formation and nuclear β-catenin positivity are characteristic. Immunohistochemically, ICTNs are diffusely positive for MUC6 and frequently positive for MUC1, whereas MUC2, MUC5AC, and CDX2 are typically absent [157]. Unlike ICPNs, background mucosal dysplasia is typically absent.
Figure 11.
Intracholecystic tubular neoplasm with low-grade intraepithelial neoplasia. (a) A large multinodular lesion is present in the body and fundus of the gallbladder. (b) Uniform, back-to-back tubules with pyloric gland differentiation are present (hematoxylin and eosin stain, ×100).
3.5.4. Differential Diagnosis
Differential diagnoses include polypoid pyloric gland metaplasia, IPNB, and invasive carcinoma. ICPNs with gastric differentiation must be distinguished from polypoid pyloric gland metaplasia, which arises in the chronically injured gallbladder as a small polypoid lesion composed of pyloric glands without complex papillary architecture. By definition, ICPN requires either a discrete nodule >10 mm or high-grade dysplasia. IPNB with gastric differentiation arises within the bile ducts and is often associated with mucin hypersecretion and ductal dilatation and frequently harbors KRAS and GNAS mutations, whereas ICNs exhibit more heterogeneous molecular features. Extension of ICNs into the Rokitansky–Aschoff sinuses may mimic invasion; in contrast, true invasive carcinoma shows irregularly angulated, infiltrative glands with marked cytologic atypia and a desmoplastic stromal reaction.
3.5.5. Key Updates in the 6th WHO Classification
According to WHO DST6, mass-forming intraepithelial neoplasms of the gallbladder are formally designated as ICNs and subclassified into ICPN and ICTN. The term “pyloric gland adenoma (PGA)” is no longer recommended, as these lesions are now largely incorporated into the gastric subtype of ICPNs [2].
Table 3 summarizes the clinicopathological and molecular features of benign biliary tumors and precursor neoplasms in the gallbladder and extrahepatic bile ducts.
Table 3.
Clinicopathological and molecular features of benign biliary tumors and precursor neoplasms in the gallbladder and extrahepatic bile ducts.
4. Pathological Diagnostic Approach
Accurate diagnosis of benign biliary tumors and precursor neoplasms requires appropriate specimen handling, adequate sampling, and systematic histopathological evaluation integrated with clinicoradiological findings.
4.1. Specimen Handling and Clinicoradiologic Correlation
For biopsy specimens, gross features, including size, color, and consistency, should be carefully documented when available. Specimens should be submitted primarily for routine histopathological examination, with representative tissue retained for ancillary studies as needed. Hematoxylin and eosin (H&E) staining remains the cornerstone of histological evaluation. Serial step sections are recommended to detect subtle architectural abnormalities and to facilitate additional histochemical and immunohistochemical studies if needed. In selected cases, fresh tissue may be submitted for molecular or ultrastructural analysis.
In surgical resection specimens, such as hepatectomy specimens, proper orientation, accurate measurement, and margin assessment are essential. Margins should be identified and inked. Lesions should be evaluated for number, size, color, consistency, presence of necrosis, proximity to margins, and background parenchymal changes. Adequate sampling is critical and should include at least one section per centimeter of tumor, with additional sampling of architecturally heterogeneous regions and tumor–non-neoplastic transition zones. As precursor neoplasms may harbor occult foci of invasion, thorough histological evaluation of all sampled sections is essential to exclude invasive carcinoma [40].
Integration of clinical and radiological information is indispensable for accurate pathological interpretation. Key factors include patient demographics (e.g., female predominance in MCN), lesion location (intrahepatic vs. extrahepatic), imaging features (e.g., ductal communication, cystic architecture, or solid components), and associated conditions (e.g., hepatolithiasis, chronic inflammation). Together, these features provide essential context for narrowing the differential diagnosis.
4.2. Histopathological Evaluation
Careful evaluation of H&E-stained sections remains the most critical diagnostic step. At low magnification, the presence of lesional tissue should first be confirmed, followed by evaluation of overall architecture, including circumscription, relationship to adjacent bile ducts, and growth pattern (e.g., nodular, cystic, intraductal, or mass-forming). At high magnification, detailed evaluation of epithelial cytology, degree of atypia, mitotic activity, and stromal features—such as fibrosis, ovarian-type stroma, or inflammatory infiltrates—is essential to distinguish benign lesions from precursor or malignant counterparts. Figure 12 presents a practical histopathological diagnostic algorithm for the differential diagnosis of hepatic cystic lesions based on epithelial lining, morphologic features, and neoplastic potential. When applying this diagnostic algorithm, key histopathological criteria should be evaluated stepwise to facilitate accurate diagnosis. After the initial distinction between epithelial-lined and non-epithelial-lined lesions, epithelial-lined lesions should be further assessed for differentiation type, ductal communication, stromal characteristics, and growth pattern. Ductal communication and intraductal growth favor IPNB, ITPN, or IOPN, whereas ovarian-type stroma in the absence of ductal communication supports the diagnosis of MCN. Architectural pattern, mucin production, oncocytic cytology, and the degree of cytological atypia are essential for further subclassification. Finally, a desmoplastic stromal reaction, irregular invasion, or a dominant parenchymal mass should prompt careful evaluation for associated invasive carcinoma or metastatic disease. The integration of these findings provides a practical framework for the differential diagnosis of hepatic cystic and intraductal biliary lesions. Thus, when the classification of a hepatic cystic lesion is uncertain, the algorithm can be applied in a stepwise manner to refine the differential diagnosis and facilitate lesion categorization.
Figure 12.
Diagnostic algorithm for hepatic cystic lesions. Hepatic cystic lesions are initially classified according to the presence or absence of an epithelial lining. Epithelial-lined lesions are further categorized by epithelial differentiation into cuboidal/low columnar, foregut/Müllerian, and biliary/mucinous/oncocytic types. Biliary/mucinous/oncocytic lesions are subsequently subdivided according to the presence of ovarian-type stroma and papillary or tubulopapillary proliferation. This facilitates the histopathological differential diagnosis of mucinous cystic neoplasm (MCN), intraductal papillary neoplasm of the bile ducts (IPNB), intraductal tubulopapillary neoplasm (ITPN) of the bile ducts, and intraductal oncocytic papillary neoplasm (IOPN) of the bile ducts. Non-epithelial-lined lesions are classified into non-neoplastic (infectious or traumatic/reactive) and neoplastic (benign or malignant) cystic lesions. AMEA, amebic abscess; CAHE, cavernous hemangioma; CDBD, cystic dilatation of the bile duct; CHFC, ciliated hepatic foregut cyst; CLDC, choledochal cyst; EMSA, embryonal sarcoma of the liver; ENMC, endometriotic cyst; FBRC, fibrous cyst; FPCL, fibropolycystic liver disease; FUGA, fungal abscess; HEMA, hematoma; HYDC, hydatid cyst; MESH, mesenchymal hamartoma; METC, metastatic tumors with cystic change; MTCC, malignant tumors with cystic change; PSDC, pseudocyst; PYGA, pyogenic abscess; SBDC, solitary bile duct cyst. This figure was created by the author solely for illustrative purposes and does not include any patient data or previously unpublished data.
Despite advances in morphological classification, the evaluation of benign and premalignant biliary lesions remains challenging due to overlapping histologic features and the inability of limited biopsy specimens to adequately represent architectural complexity or stromal invasion. When diagnostic uncertainty persists, a conservative interpretation combined with close clinical follow-up and multidisciplinary correlation should be considered.
IHC serves as an important ancillary tool, particularly in diagnostically challenging cases. Markers such as CK7 and CK19 support biliary differentiation, whereas p53, Ki-67, and SMAD4 aid in assessing dysplasia and malignant transformation. PR immunostaining is useful in differentiating endometriotic cysts from MCN (Figure 13). Mucin core proteins (MUC1, MUC2, MUC5AC, and MUC6) and CDX2 help define the epithelial phenotypes of intraductal neoplasms and may support their subclassification into pancreaticobiliary, intestinal, gastric, or pyloric gland differentiation. Furthermore, CK7/CK20 immunohistochemistry aids in distinguishing metastatic colonic adenocarcinoma from primary biliary tumors (Figure 14). In practice, these markers should be selected according to the specific diagnostic question, such as confirming biliary lineage, identifying ovarian-type stroma, subclassifying intraductal neoplasms, evaluating high-grade dysplasia or invasion, or ruling out metastatic disease. However, because no single marker is entirely specific, IHC findings should always be interpreted in the context of histomorphology. Table 4 summarizes the immunohistochemical markers useful for the diagnosis of benign biliary neoplasms and precursor neoplasms.
Figure 13.
Endometriotic cyst. (a) The inner surface of the cystic lesion is brown-tan and hemorrhagic. (b) The lesion is composed of epithelium and stroma (left). Both epithelial and stromal cells are positive for progesterone receptor (PR) (right). PR positivity in glandular epithelial cells is useful for distinguishing an endometriotic cyst from a mucinous cystic neoplasm (hematoxylin and eosin stain [left] and immunohistochemical stain [right], ×200).
Figure 14.
Metastatic colonic adenocarcinoma with intrabiliary growth. (a) A transition between the intrabiliary carcinoma and the adjacent non-neoplastic biliary epithelium is present (hematoxylin and eosin stain, ×100). (b) The non-neoplastic biliary epithelium is positive for cytokeratin 7 (left), whereas the intrabiliary carcinoma is positive for cytokeratin 20 (right), supporting the diagnosis of metastatic colonic adenocarcinoma (immunohistochemical stain, ×200).
Table 4.
Immunohistochemical markers for the diagnosis of benign biliary tumors and precursor neoplasms of the bile ducts.
Molecular analysis provides additional diagnostic and pathogenetic insight in selected cases. Recurrent alterations include KRAS and GNAS mutations in IPNBs, PRKACA/PRKACB fusions in IOPNs, and KRAS-associated progression in MCNs; in contrast, many benign lesions lack identifiable driver mutations. Accurate diagnosis requires integration of histopathological, immunophenotypic, molecular, and clinicoradiologic findings within a multidisciplinary diagnostic framework.
5. Future Perspectives
Several diagnostic challenges highlighted throughout this review remain unresolved, particularly distinguishing REA from BilIN, BDA from well-differentiated SD-iCCA, and BAF from tubulocystic variants of iCCA, especially in limited biopsy specimens. Integration of histopathologic, immunohistochemical, molecular, and radiologic findings will likely become increasingly important for addressing these diagnostic dilemmas and improving the classification and risk stratification of biliary precursor lesions.
Recent advances have substantially improved our understanding of benign biliary tumors and precursor neoplasms; however, their broader molecular landscape and stepwise tumorigenic mechanisms remain incompletely defined. Multi-omics (genomic, epigenomic, and transcriptomic) approaches are expected to refine tumor classification and risk stratification. The tumor immune microenvironment has emerged as a critical component of biliary tumorigenesis; however, its role in biliary precursor neoplasms remains less well defined than in iCCA [164]. A deeper understanding of interactions among the biliary epithelium, stroma, and immune cells may reveal potential targets for chemoprevention and early therapeutic intervention.
Advances in next-generation sequencing (NGS) and spatially resolved omics technologies are expected to further elucidate the molecular evolution from benign lesions to invasive carcinoma. Single-cell and spatial transcriptomic approaches can provide insights into clonal relationships, intralesional heterogeneity, and tumor microenvironmental interactions [165]. From a diagnostic perspective, future biomarker development should focus on identifying highly reproducible ancillary markers that enable reliable distinction between REA and BilIN, as well as between benign biliary lesions and early invasive CCA. For example, integrating NGS-based chromatin-remodeling gene panels and entity-specific fusion analyses may facilitate the classification and risk stratification of biliary precursor neoplasms, particularly as precision oncology continues to expand in hepatobiliary malignancies [166,167]. In parallel, AI-assisted digital pathology platforms may prove particularly valuable in resolving diagnostically challenging cases, especially when evaluating limited biopsy specimens. Such deep-learning approaches have the potential to improve diagnostic reproducibility, efficiency, and workflow management in borderline lesions requiring extensive histologic assessment [168,169,170]. Moreover, recent studies have demonstrated the feasibility of AI-assisted histopathological systems for predicting molecular alterations directly from tumor morphology in iCCA, highlighting their potential role in precision diagnostics [171]. Continued refinement of biliary classification systems will be necessary to harmonize terminology across the pancreaticobiliary system. Close multidisciplinary collaboration among pathologists, clinicians, radiologists, and molecular scientists will be critical to translate these advances into improved patient care and clinical outcomes.
6. Conclusions
Benign biliary tumors and precursor neoplasms comprise a heterogeneous group of entities with distinct morphological, immunophenotypic, and molecular features. Their clinical significance lies in their broad biological spectrum, ranging from entirely benign lesions to well-defined precursors of invasive carcinoma. The 2026 WHO classification provides an updated framework for their systematic diagnosis, integrating histopathological, immunophenotypic, and molecular criteria. Further studies are needed to elucidate the molecular mechanisms driving progression to invasive carcinoma and to identify biomarkers for early detection and risk stratification.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Data Availability Statement
All data were included in the manuscript.
Acknowledgments
The research support team at Yeungnam University College of Medicine supported the medical illustration for this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AI | Artificial intelligence |
| AMEA | Amebic abscess |
| APC | Adenomatous polyposis coli |
| ARID1A | AT-rich interaction domain-containing protein 1A |
| ARID2 | AT-rich interaction domain-containing protein 2 |
| ATM | Ataxia telangiectasia mutated |
| AUPBD | Anomalous union of the pancreaticobiliary ducts |
| BAF | Biliary adenofibroma |
| BAP1 | BRCA1-associated protein 1 |
| BDA | Bile duct adenoma |
| BilIN | Biliary intraepithelial neoplasia |
| BRCA2 | Breast cancer susceptibility gene 2 |
| CA19-9 | Carbohydrate antigen 19-9 |
| CAHE | Cavernous hemangioma |
| CCA | Cholangiocarcinoma |
| CD117 | Cluster of differentiation 117 |
| CDBD | Cystic dilatation of the bile duct |
| CDH1 | Cadherin 1 |
| CDKN2A | Cyclin-dependent kinase inhibitor 2A |
| CDX2 | Caudal type homeobox 2 |
| CEA | Carcinoembryonic antigen |
| CHFC | Ciliated hepatic foregut cyst |
| CK | Cytokeratin |
| CLDC | Choledochal cyst |
| CRP | C-reactive protein |
| CTNNB1 | Catenin beta 1 |
| DCC | Deleted in colorectal carcinoma |
| DNAJB1 | DnaJ heat shock protein family (Hsp40) member B1 |
| DR | Ductular reaction |
| EMA | Epithelial membrane antigen |
| EMSA | Embryonal sarcoma of the liver |
| ENMC | Endometriotic cyst |
| ER | Estrogen receptor |
| ERBB2 | Erb-b2 receptor tyrosine kinase 2 |
| ERBB3 | Erb-b3 receptor tyrosine kinase 3 |
| EZH2 | Enhancer of zeste homolog 2 |
| FBRC | Fibrous cyst |
| FGFR | Fibroblast growth factor receptor |
| FGFR2 | Fibroblast growth factor receptor 2 |
| FHIT | Fragile histidine triad |
| FPCL | Fibropolycystic liver disease |
| FUGA | Fungal abscess |
| GNAS | Guanine nucleotide-binding protein, alpha-stimulating |
| H&E | Hematoxylin and eosin |
| HEMA | Hematoma |
| Hep Par-1 | Hepatocyte paraffin 1 |
| HYDC | Hydatid cyst |
| iCCA | Intrahepatic cholangiocarcinoma |
| ICN | Intracholecystic neoplasm |
| ICPN | Intracholecystic papillary neoplasm |
| ICTN | Intracholecystic tubular neoplasm |
| IDH | Isocitrate dehydrogenase |
| IDH1 | Isocitrate dehydrogenase 1 |
| IDH2 | Isocitrate dehydrogenase 2 |
| IHC | Immunohistochemistry |
| IOPN | Intraductal oncocytic papillary neoplasm |
| IPNB | Intraductal papillary neoplasm of the bile ducts |
| ISH | In situ hybridization |
| ITPN | Intraductal tubulopapillary neoplasm |
| KIT | KIT proto-oncogene receptor tyrosine kinase |
| Ki-67 | Ki-67 antigen |
| KMT2C | Lysine methyltransferase 2C |
| KRAS | KRAS proto-oncogene, GTPase |
| LD-iCCA | Large-duct type intrahepatic cholangiocarcinoma |
| MCN | Mucinous cystic neoplasm |
| MESH | Mesenchymal hamartoma |
| METC | Metastatic tumors with cystic change |
| MTCC | Malignant tumors with cystic change |
| MUC | Mucin |
| MUC1 | Mucin 1 |
| MUC2 | Mucin 2 |
| MUC5AC | Mucin 5AC |
| MUC6 | Mucin 6 |
| N:C ratio | Nuclear-to-cytoplasmic |
| NET | Neuroendocrine tumor |
| NFE2L2 | Nuclear factor erythroid 2-related factor 2 |
| NGS | Next-generation sequencing |
| NRAS | NRAS proto-oncogene, GTPase |
| PBM | Pancreaticobiliary maljunction |
| PBRM1 | Polybromo 1 |
| PGA | Pyloric gland adenoma |
| PIK3CA | Phosphatidylinositol-4,5-bisphosphate 3-kinase catalytic subunit alpha |
| PR | Progesterone receptor |
| PRKACA | Protein kinase cAMP-activated catalytic subunit alpha |
| PRKACB | Protein kinase cAMP-activated catalytic subunit beta |
| PSC | Primary sclerosing cholangitis |
| PSDC | Pseudocyst |
| PYGA | Pyogenic abscess |
| RB1 | RB transcriptional corepressor 1 |
| REA | Reactive epithelial atypia |
| RNF43 | Ring finger protein 43 |
| S100P | S100 calcium-binding protein P |
| SATB2 | SATB homeobox 2 |
| SBDC | Solitary bile duct cyst |
| SD-iCCA | Small-duct type intrahepatic cholangiocarcinoma |
| SMAD4 | SMAD family member 4 |
| SMARCA4 | SWI/SNF-related, matrix-associated, actin-dependent regulator of chromatin subfamily A member 4 |
| SWI/SNF | SWItch/Sucrose Non-Fermentable chromatin-remodeling complex |
| TP53 | Tumor protein p53 |
| VMC | Von Meyenburg complex |
| WHO | World Health Organization |
| WHO DST6 | Sixth edition World Health Organization Classification of Digestive System Tumours |
References
- WHO Classification of Tumours Editorial Board. Digestive System Tumours, 6th ed.; WHO Classification of Tumours Series; [Internet; Beta Version Ahead of Print]; International Agency for Research on Cancer: Lyon, France, 2026; Volume 1, Available online: https://tumourclassification.iarc.who.int/chapters/72 (accessed on 25 April 2026).
- Arends, M.J.; Esposito, I.; Gill, A.J.; Hruban, R.H.; Khoury, J.D.; Kojima, M.; Montgomery, E.A.; Abdulkareem, F.; Carneiro, F.; Costamagna, G.; et al. Changes in the 6th edition of the World Health Organization classification of tumours of the digestive system. Histopathology 2026, 88, 1295–1314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Kakuda, Y.; Uesaka, K. Characterization of intraductal papillary neoplasm of the bile duct with respect to the histopathologic similarities to pancreatic intraductal papillary mucinous neoplasm. Gut Liver 2019, 13, 617–627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, W.; Xue, Y. Epithelial precursor lesions of the bile duct. Semin. Diagn. Pathol. 2025, 42, 150961. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bray, F.; Laversanne, M.; Sung, H.; Ferlay, J.; Siegel, R.L.; Soerjomataram, I.; Jemal, A. Global cancer statistics 2022: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J. Clin. 2024, 74, 229–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schlitter, A.M.; Born, D.; Bettstetter, M.; Specht, K.; Kim-Fuchs, C.; Riener, M.O.; Jeliazkova, P.; Sipos, B.; Siveke, J.T.; Terris, B.; et al. Intraductal papillary neoplasms of the bile duct: Stepwise progression to carcinoma involves common molecular pathways. Mod. Pathol. 2014, 27, 73–86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Kakuda, Y.; Sugino, T.; Sato, Y.; Fukumura, Y. Pathologies of precursor lesions of biliary tract carcinoma. Cancers 2022, 14, 5358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xue, Y.; Basturk, O. Intraductal neoplasms of the pancreatobiliary tract: Navigating the alphabet. Histopathology 2023, 83, 499–508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, C.; Rullis, I.; Rogers, L.S. Bile duct adenomas as liver nodules. Arch. Surg. 1978, 113, 272–274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aishima, S.; Tanaka, Y.; Kubo, Y.; Shirabe, K.; Maehara, Y.; Oda, Y. Bile duct adenoma and von Meyenburg complex-like duct arising in hepatitis and cirrhosis: Pathogenesis and histological characteristics. Pathol. Int. 2014, 64, 551–559. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allaire, G.S.; Rabin, L.; Ishak, K.G.; Sesterhenn, I.A. Bile duct adenoma. A study of 152 cases. Am. J. Surg. Pathol. 1988, 12, 708–715. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhathal, P.S.; Hughes, N.R.; Goodman, Z.D. The so-called bile duct adenoma is a peribiliary gland hamartoma. Am. J. Surg. Pathol. 1996, 20, 858–864. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pinho, A.C.; Melo, R.B.; Oliveira, M.; Almeida, M.; Lopes, J.; Graça, L.; Costa-Maia, J. Adenoma-carcinoma sequence in intrahepatic cholangiocarcinoma. Int. J. Surg. Case Rep. 2012, 3, 131–133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hasebe, T.; Sakamoto, M.; Mukai, K.; Kawano, N.; Konishi, M.; Ryu, M.; Fukamachi, S.; Hirohashi, S. Cholangiocarcinoma arising in bile duct adenoma with focal area of bile duct hamartoma. Virchows Arch. 1995, 426, 209–213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pujals, A.; Amaddeo, G.; Castain, C.; Bioulac-Sage, P.; Compagnon, P.; Zucman-Rossi, J.; Azoulay, D.; Leroy, K.; Zafrani, E.S.; Calderaro, J. BRAF V600E mutations in bile duct adenomas. Hepatology 2015, 61, 403–405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pujals, A.; Bioulac-Sage, P.; Castain, C.; Charpy, C.; Zafrani, E.S.; Calderaro, J. BRAF V600E mutational status in bile duct adenomas and hamartomas. Histopathology 2015, 67, 562–567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hughes, N.R.; Goodman, Z.D.; Bhathal, P.S. An immunohistochemical profile of the so-called bile duct adenoma: Clues to pathogenesis. Am. J. Surg. Pathol. 2010, 34, 1312–1318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Albores-Saavedra, J.; Hoang, M.P.; Murakata, L.A.; Sinkre, P.; Yaziji, H. Atypical bile duct adenoma, clear cell type: A previously undescribed tumor of the liver. Am. J. Surg. Pathol. 2001, 25, 956–960. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arena, V.; Arena, E.; Stigliano, E.; Capelli, A. Bile duct adenoma with oncocytic features. Histopathology 2006, 49, 318–320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsokos, C.G.; Krings, G.; Yilmaz, F.; Ferrell, L.D.; Gill, R.M. Proliferative index facilitates distinction between benign biliary lesions and intrahepatic cholangiocarcinoma. Hum. Pathol. 2016, 57, 61–67. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sasaki, M.; Matsubara, T.; Kakuda, Y.; Sato, Y.; Nakanuma, Y. Immunostaining for polycomb group protein EZH2 and senescent marker p16INK4a may be useful to differentiate cholangiolocellular carcinoma from ductular reaction and bile duct adenoma. Am. J. Surg. Pathol. 2014, 38, 364–369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moy, A.P.; Arora, K.; Deshpande, V. Albumin expression distinguishes bile duct adenomas from metastatic adenocarcinoma. Histopathology 2016, 69, 423–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gurrera, A.; Alaggio, R.; Leone, G.; Aprile, G.; Magro, G. Biliary adenofibroma of the liver: Report of a case and review of the literature. Pathol. Res. Int. 2010, 2010, 504584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arnason, T.; Borger, D.R.; Corless, C.; Hagen, C.; Iafrate, A.J.; Makhlouf, H.; Misdraji, J.; Sapp, H.; Tsui, W.M.; Wanless, I.R.; et al. Biliary adenofibroma of liver: Morphology, tumor genetics, and outcomes in 6 cases. Am. J. Surg. Pathol. 2017, 41, 499–505. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, X.; Zhang, X. Hepatic biliary adenofibroma: Histological characteristics, diagnostic challenges, and its role as a precursor to intrahepatic cholangiocarcinoma. J. Clin. Transl. Pathol. 2024, 4, 163–167. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, W.; Zhao, Y.; Liu, Y.; Hua, Z.; Liu, A. Imaging features of biliary adenofibroma of the liver with malignant transformation: A case report with literature review. BMC Med. Imaging 2022, 22, 47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sturm, A.K.; Welsch, T.; Meissner, C.; Aust, D.E.; Baretton, G. A case of biliary adenofibroma of the liver with malignant transformation: A morphomolecular case report and review of the literature. Surg. Case Rep. 2019, 5, 104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thompson, S.M.; Zendejas-Mummert, B.; Hartgers, M.L.; Venkatesh, S.K.; Smyrk, T.C.; Mahipal, A.; Smoot, R.L. Malignant transformation of biliary adenofibroma: A rare biliary cystic tumor. J. Gastrointest. Oncol. 2016, 7, E107–E112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alshbib, A.; Grzyb, K.; Syversveen, T.; Reims, H.M.; Lassen, K.; Yaqub, S. Biliary adenofibroma: A rare liver tumor with transition to invasive carcinoma. Case Rep. Surg. 2022, 2022, 5280884. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, N.T.; Harring, T.R.; Holley, L.; Goss, J.A.; O’Mahony, C.A. Biliary adenofibroma with carcinoma in situ: A rare case report. Case Rep. Hepatol. 2012, 2012, 793963. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsutsui, A.; Bando, Y.; Sato, Y.; Miyake, H.; Sawada-Kitamura, S.; Shibata, H.; Kakuda, Y.; Harada, K.; Sasaki, M.; Nakanuma, Y. Biliary adenofibroma with ominous features of imminent malignant changes. Clin. J. Gastroenterol. 2014, 7, 441–448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thai, E.; Dalla Valle, R.; Evaristi, F.; Silini, E.M. A case of biliary adenofibroma with malignant transformation. Pathol. Res. Pract. 2016, 212, 468–470. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Godambe, A.; Brunt, E.M.; Fulling, K.H.; Reza Kermanshahi, T. Biliary adenofibroma with invasive carcinoma: Case report and review of the literature. Case Rep. Pathol. 2016, 2016, 8068513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaminsky, P.; Preiss, J.; Sasatomi, E.; Gerber, D.A. Biliary adenofibroma: A rare hepatic lesion with malignant features. Hepatology 2017, 65, 380–383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y. Intrahepatic cholangiocarcinoma: Typical features, uncommon variants, and controversial related entities. Hum. Pathol. 2023, 132, 197–207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Masetto, F.; Mafficini, A.; Saka, B.; Armutlu, A.; Chatterjee, D.; Jang, K.T.; Zen, Y.; Navale, P.; Fassan, M.; Bacchi, C.E.; et al. Tubulocystic carcinoma of bile ducts: A distinct type of cholangiocarcinoma associated with adenofibroma-type lesions. Am. J. Surg. Pathol. 2024, 48, 1082–1092. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y.; Pedica, F.; Patcha, V.R.; Capelli, P.; Zamboni, G.; Casaril, A.; Quaglia, A.; Nakanuma, Y.; Heaton, N.; Portmann, B. Mucinous cystic neoplasms of the liver: A clinicopathological study and comparison with intraductal papillary neoplasms of the bile duct. Mod. Pathol. 2011, 24, 1079–1089. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Devaney, K.; Goodman, Z.D.; Ishak, K.G. Hepatobiliary cystadenoma and cystadenocarcinoma. A light microscopic and immunohistochemical study of 70 patients. Am. J. Surg. Pathol. 1994, 18, 1078–1091. [Google Scholar] [PubMed]
- Armutlu, A.; Quigley, B.; Choi, H.; Basturk, O.; Akkas, G.; Pehlivanoglu, B.; Memis, B.; Jang, K.T.; Erkan, M.; Erkan, B.; et al. Hepatic cysts: Reappraisal of the classification, terminology, differential diagnosis, and clinicopathologic characteristics in 258 cases. Am. J. Surg. Pathol. 2022, 46, 1219–1233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quigley, B.; Reid, M.D.; Pehlivanoglu, B.; Squires, M.H., 3rd; Maithel, S.; Xue, Y.; Choi, H.J.; Akkas, G.; Muraki, T.; Kooby, D.A.; et al. Hepatobiliary mucinous cystic neoplasms with ovarian type stroma (so-called “hepatobiliary cystadenoma/cystadenocarcinoma”): Clinicopathologic analysis of 36 cases illustrates rarity of carcinomatous change. Am. J. Surg. Pathol. 2018, 42, 95–102. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fujikura, K.; Akita, M.; Abe-Suzuki, S.; Itoh, T.; Zen, Y. Mucinous cystic neoplasms of the liver and pancreas: Relationship between KRAS driver mutations and disease progression. Histopathology 2017, 71, 591–600. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sugawara, S.; Hirai, I.; Watanabe, T.; Tezuka, K.; Kimura, W. A case of mucinous cystic neoplasm of the gallbladder. Clin. J. Gastroenterol. 2018, 11, 428–432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zevallos Quiroz, J.C.; Jiménez Agüero, R.; Garmendi Irizar, M.; Ruiz Montesinos, I.; Comba Miranda, J.W. Mucinous cystic neoplasm of the gallbladder obstructing the common bile duct, a rare entity with a new name. Cir. Esp. 2014, 92, 567–569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, C.W.; Tsai, H.I.; Lin, Y.S.; Wu, T.H.; Yu, M.C.; Chen, M.F. Intrahepatic biliary mucinous cystic neoplasms: Clinicoradiological characteristics and surgical results. BMC Gastroenterol. 2015, 15, 67. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koffron, A.; Rao, S.; Ferrario, M.; Abecassis, M. Intrahepatic biliary cystadenoma: Role of cyst fluid analysis and surgical management in the laparoscopic era. Surgery 2004, 136, 926–936. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Safari, M.T.; Shahrokh, S.; Miri, M.B.; Foroughi, F.; Sadeghi, A. Biliary mucinous cystic neoplasm: A case report and review of the literature. Gastroenterol. Hepatol. Bed Bench 2016, 9, S88–S92. [Google Scholar] [PubMed]
- Jeong, D.; Jiang, K.; Anaya, D.A. Mucinous cystic neoplasm of the liver masquerading as an echinococcal cyst: Radiologic-pathologic differential of complex cystic liver lesions. J. Clin. Imaging Sci. 2016, 6, 12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Furumaya, A.; Schulz, H.H.; Verheij, J.; Takkenberg, R.B.; Besselink, M.G.; Kazemier, G.; Erdmann, J.I.; van Delden, O.M. Diagnosis and treatment of patients with suspected mucinous cystic neoplasms of the liver: A retrospective cohort study. Langenbecks Arch. Surg. 2024, 409, 66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Treeck, B.J.; Lotfalla, M.; Czeczok, T.W.; Mounajjed, T.; Moreira, R.K.; Allende, D.S.; Reid, M.D.; Naini, B.V.; Westerhoff, M.; Adsay, N.V.; et al. Molecular and immunohistochemical analysis of mucinous cystic neoplasm of the liver. Am. J. Clin. Pathol. 2020, 154, 837–847. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sung, Y.N.; Stojanova, M.; Shin, S.; Cho, H.; Heaphy, C.M.; Hong, S.M. Gradual telomere shortening in the tumorigenesis of pancreatic and hepatic mucinous cystic neoplasms. Hum. Pathol. 2024, 152, 105653. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elias, K.M.; Tsantoulis, P.; Tille, J.C.; Vitonis, A.; Doyle, L.A.; Hornick, J.L.; Kaya, G.; Barnes, L.; Cramer, D.W.; Puppa, G.; et al. Primordial germ cells as a potential shared cell of origin for mucinous cystic neoplasms of the pancreas and mucinous ovarian tumors. J. Pathol. 2018, 246, 459–469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Albores-Saavedra, J.; Córdova-Ramón, J.C.; Chablé-Montero, F.; Dorantes-Heredia, R.; Henson, D.E. Cystadenomas of the liver and extrahepatic bile ducts: Morphologic and immunohistochemical characterization of the biliary and intestinal variants. Ann. Diagn. Pathol. 2015, 19, 124–129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Terada, T.; Kitamura, Y.; Ohta, T.; Nakanuma, Y. Endocrine cells in hepatobiliary cystadenomas and cystadenocarcinomas. Virchows Arch. 1997, 430, 37–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsu, M.; Terris, B.; Wu, T.T.; Zen, Y.; Eng, H.L.; Huang, W.T.; Yeh, M.M. Endometrial cysts within the liver: A rare entity and its differential diagnosis with mucinous cystic neoplasms of the liver. Hum. Pathol. 2014, 45, 761–767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koshiol, J.; Bellolio, E.; Vivallo, C.; Cook, P.; Roa, J.C.; McGee, E.E.; Losada, H.; Van Dyke, A.L.; Van De Wyngard, V.; Prado, R.; et al. Distribution of dysplasia and cancer in the gallbladder: An analysis from a high cancer-risk population. Hum. Pathol. 2018, 82, 87–94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roa, I.; de Aretxabala, X.; Araya, J.C.; Roa, J. Preneoplastic lesions in gallbladder cancer. J. Surg. Oncol. 2006, 93, 615–623. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Sugino, T.; Okamura, Y.; Nomura, Y.; Watanabe, H.; Terada, T.; Sato, Y. Characterization of high-grade biliary intraepithelial neoplasm of the gallbladder in comparison with intracholecystic papillary neoplasm. Hum. Pathol. 2021, 116, 22–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, W.J.; Wolff, E.; Varma, C.R.; Shoela, R. Biliary intraepithelial neoplasia with gallbladder adenoma and cirrhosis: A case report. Cureus 2022, 14, e27780. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lewis, J.T.; Talwalkar, J.A.; Rosen, C.B.; Smyrk, T.C.; Abraham, S.C. Prevalence and risk factors for gallbladder neoplasia in patients with primary sclerosing cholangitis: Evidence for a metaplasia-dysplasia-carcinoma sequence. Am. J. Surg. Pathol. 2007, 31, 907–913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lewis, J.T.; Talwalkar, J.A.; Rosen, C.B.; Smyrk, T.C.; Abraham, S.C. Precancerous bile duct pathology in end-stage primary sclerosing cholangitis, with and without cholangiocarcinoma. Am. J. Surg. Pathol. 2010, 34, 27–34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.E.; Jang, J.Y.; Lee, Y.J.; Choi, D.W.; Lee, W.J.; Cho, B.H.; Kim, S.W. Choledochal cyst and associated malignant tumors in adults: A multicenter survey in South Korea. Arch. Surg. 2011, 146, 1178–1184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Noda, Y.; Fujita, N.; Kobayashi, G.; Ito, K.; Horaguchi, J.; Takasawa, O.; Obana, T.; Ishida, K.; Senoo, S.; Yonechi, M.; et al. Histological study of gallbladder and bile duct epithelia in patients with anomalous arrangement of the pancreaticobiliary ductal system: Comparison between those with and without a dilated common bile duct. J. Gastroenterol. 2007, 42, 211–218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sithithaworn, P.; Yongvanit, P.; Duenngai, K.; Kiatsopit, N.; Pairojkul, C. Roles of liver fluke infection as risk factor for cholangiocarcinoma. J. Hepatobiliary Pancreat. Sci. 2014, 21, 301–308. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, R.; Song, Y.; Hua, R.; Ahmed, S.; Xie, Y.; Lai, C.; Xu, J.; Li, F.; Li, Y.; Li, Z.; et al. Cell-free DNA in plasma reveals genomic similarity between biliary tract inflammatory lesion and biliary tract cancer. Phenomics 2024, 4, 339–351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, J.; Peng, X.; Dong, K.; Long, J.; Guo, X.; Li, H.; Bai, Y.; Yang, X.; Wang, D.; Lu, X.; et al. Genomic characterization of co-existing neoplasia and carcinoma lesions reveals distinct evolutionary paths of gallbladder cancer. Nat. Commun. 2021, 12, 4753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roa, J.C.; García, P.; Kapoor, V.K.; Maithel, S.K.; Javle, M.; Koshiol, J. Gallbladder cancer. Nat. Rev. Dis. Primers 2022, 8, 69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanishi, Y.; Zen, Y.; Kondo, S.; Itoh, T.; Itatsu, K.; Nakanuma, Y. Expression of cell cycle-related molecules in biliary premalignant lesions: Biliary intraepithelial neoplasia and biliary intraductal papillary neoplasm. Hum. Pathol. 2008, 39, 1153–1161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsu, M.; Sasaki, M.; Igarashi, S.; Sato, Y.; Nakanuma, Y. KRAS and GNAS mutations and p53 overexpression in biliary intraepithelial neoplasia and intrahepatic cholangiocarcinomas. Cancer 2013, 119, 1669–1674. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sasaki, M.; Nitta, T.; Sato, Y.; Nakanuma, Y. Autophagy may occur at an early stage of cholangiocarcinogenesis via biliary intraepithelial neoplasia. Hum. Pathol. 2015, 46, 202–209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basturk, O.; Hong, S.M.; Wood, L.D.; Adsay, N.V.; Albores-Saavedra, J.; Biankin, A.V.; Brosens, L.A.; Fukushima, N.; Goggins, M.; Hruban, R.H.; et al. A revised classification system and recommendations from the Baltimore consensus meeting for neoplastic precursor lesions in the pancreas. Am. J. Surg. Pathol. 2015, 39, 1730–1741. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y.; Aishima, S.; Ajioka, Y.; Haratake, J.; Kage, M.; Kondo, F.; Nimura, Y.; Sakamoto, M.; Sasaki, M.; Shimamatsu, K.; et al. Proposal of histological criteria for intraepithelial atypical/proliferative biliary epithelial lesions of the bile duct in hepatolithiasis with respect to cholangiocarcinoma: Preliminary report based on interobserver agreement. Pathol. Int. 2005, 55, 180–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roa, J.C.; Basturk, O.; Adsay, V. Dysplasia and carcinoma of the gallbladder: Pathological evaluation, sampling, differential diagnosis and clinical implications. Histopathology 2021, 79, 2–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matthaei, H.; Lingohr, P.; Strässer, A.; Dietrich, D.; Rostamzadeh, B.; Glees, S.; Roering, M.; Möhring, P.; Scheerbaum, M.; Stoffels, B.; et al. Biliary intraepithelial neoplasia (BilIN) is frequently found in surgical margins of biliary tract cancer resection specimens but has no clinical implications. Virchows Arch. 2015, 466, 133–141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shiraki, T.; Kuroda, H.; Takada, A.; Nakazato, Y.; Kubota, K.; Imai, Y. Intraoperative frozen section diagnosis of bile duct margin for extrahepatic cholangiocarcinoma. World J. Gastroenterol. 2018, 24, 1332–1342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aishima, S.; Oda, Y. Pathogenesis and classification of intrahepatic cholangiocarcinoma: Different characters of perihilar large duct type versus peripheral small duct type. J. Hepatobiliary Pancreat. Sci. 2015, 22, 94–100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aishima, S.; Iguchi, T.; Fujita, N.; Taketomi, A.; Maehara, Y.; Tsuneyoshi, M.; Oda, Y. Histological and immunohistological findings in biliary intraepithelial neoplasia arising from a background of chronic biliary disease compared with liver cirrhosis of non-biliary aetiology. Histopathology 2011, 59, 867–875. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosa, L.; Lobos-González, L.; Muñoz-Durango, N.; García, P.; Bizama, C.; Gómez, N.; González, X.; Wichmann, I.A.; Saavedra, N.; Guevara, F.; et al. Evaluation of the chemopreventive potentials of ezetimibe and aspirin in a novel mouse model of gallbladder preneoplasia. Mol. Oncol. 2020, 14, 2834–2852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Espinoza, J.A.; Bizama, C.; García, P.; Ferreccio, C.; Javle, M.; Miquel, J.F.; Koshiol, J.; Roa, J.C. The inflammatory inception of gallbladder cancer. Biochim. Biophys. Acta 2016, 1865, 245–254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wistuba, I.I.; Gazdar, A.F.; Roa, I.; Albores-Saavedra, J. p53 protein overexpression in gallbladder carcinoma and its precursor lesions: An immunohistochemical study. Hum. Pathol. 1996, 27, 360–365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oohashi, Y.; Watanabe, H.; Ajioka, Y.; Hatakeyama, K. p53 immunostaining distinguishes malignant from benign lesions of the gall-bladder. Pathol. Int. 1995, 45, 58–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sato, Y.; Harada, K.; Sasaki, M.; Nakanuma, Y. Histological characteristics of biliary intraepithelial neoplasia-3 and intraepithelial spread of cholangiocarcinoma. Virchows Arch. 2013, 462, 421–427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y.; Sasaki, M.; Fujii, T.; Chen, T.C.; Chen, M.F.; Yeh, T.S.; Jan, Y.Y.; Huang, S.F.; Nimura, Y.; Nakanuma, Y. Different expression patterns of mucin core proteins and cytokeratins during intrahepatic cholangiocarcinogenesis from biliary intraepithelial neoplasia and intraductal papillary neoplasm of the bile duct—An immunohistochemical study of 110 cases of hepatolithiasis. J. Hepatol. 2006, 44, 350–358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aishima, S.; Fujita, N.; Mano, Y.; Kubo, Y.; Tanaka, Y.; Taketomi, A.; Shirabe, K.; Maehara, Y.; Oda, Y. Different roles of S100P overexpression in intrahepatic cholangiocarcinoma: Carcinogenesis of perihilar type and aggressive behavior of peripheral type. Am. J. Surg. Pathol. 2011, 35, 590–598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sato, Y.; Harada, K.; Sasaki, M.; Nakanuma, Y. Clinicopathological significance of S100 protein expression in cholangiocarcinoma. J. Gastroenterol. Hepatol. 2013, 28, 1422–1429. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, H.; Davydova, L.; Mandich, D.; Cartun, R.W.; Ligato, S. S100A4 protein and mesothelin expression in dysplasia and carcinoma of the extrahepatic bile duct. Am. J. Clin. Pathol. 2007, 127, 374–379. [Google Scholar] [CrossRef] [PubMed]
- Albores-Saavedra, J.; Shukla, D.; Carrick, K.; Henson, D.E. In situ and invasive adenocarcinomas of the gallbladder extending into or arising from Rokitansky-Aschoff sinuses: A clinicopathologic study of 49 cases. Am. J. Surg. Pathol. 2004, 28, 621–628. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roa, J.C.; Tapia, O.; Manterola, C.; Villaseca, M.; Guzman, P.; Araya, J.C.; Bagci, P.; Saka, B.; Adsay, V. Early gallbladder carcinoma has a favorable outcome but Rokitansky-Aschoff sinus involvement is an adverse prognostic factor. Virchows Arch. 2013, 463, 651–661. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wan, X.S.; Xu, Y.Y.; Qian, J.Y.; Yang, X.B.; Wang, A.Q.; He, L.; Zhao, H.T.; Sang, X.T. Intraductal papillary neoplasm of the bile duct. World J. Gastroenterol. 2013, 19, 8595–8604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ohtsuka, M.; Shimizu, H.; Kato, A.; Yoshitomi, H.; Furukawa, K.; Tsuyuguchi, T.; Sakai, Y.; Yokosuka, O.; Miyazaki, M. Intraductal papillary neoplasms of the bile duct. Int. J. Hepatol. 2014, 2014, 459091. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, H.J.; Kim, S.Y.; Kim, H.J.; Lee, S.S.; Hong, G.S.; Byun, J.H.; Hong, S.M.; Lee, M.G. Intraductal papillary neoplasm of the bile duct: Clinical, imaging, and pathologic features. AJR Am. J. Roentgenol. 2018, 211, 67–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mocchegiani, F.; Vincenzi, P.; Conte, G.; Nicolini, D.; Rossi, R.; Cacciaguerra, A.B.; Vivarelli, M. Intraductal papillary neoplasm of the bile duct: The new frontier of biliary pathology. World J. Gastroenterol. 2023, 29, 5361–5373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aoki, Y.; Mizuma, M.; Hata, T.; Aoki, T.; Omori, Y.; Ono, Y.; Mizukami, Y.; Unno, M.; Furukawa, T. Intraductal papillary neoplasms of the bile duct consist of two distinct types specifically associated with clinicopathological features and molecular phenotypes. J. Pathol. 2020, 251, 38–48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.; Askan, G.; Ozcan, K.; Rana, S.; Zehir, A.; Bhanot, U.K.; Yantiss, R.K.; Rao, D.S.; Wahl, S.J.; Bagci, P.; et al. Tumoral intraductal neoplasms of the bile ducts comprise morphologically and genetically distinct entities. Arch. Pathol. Lab. Med. 2023, 147, 1390–1401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Jang, K.T.; Fukushima, N.; Furukawa, T.; Hong, S.M.; Kim, H.; Lee, K.B.; Zen, Y.; Jang, J.Y.; Kubota, K. A statement by the Japan-Korea expert pathologists for future clinicopathological and molecular analyses toward consensus building of intraductal papillary neoplasm of the bile duct through several opinions at the present stage. J. Hepatobiliary Pancreat. Sci. 2018, 25, 181–187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hong, G.S.; Byun, J.H.; Kim, J.H.; Kim, H.J.; Lee, S.S.; Hong, S.M.; Lee, M.G. Thread sign in biliary intraductal papillary mucinous neoplasm: A novel specific finding for MRI. Eur. Radiol. 2016, 26, 3112–3120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luvira, V.; Pugkhem, A.; Bhudhisawasdi, V.; Pairojkul, C.; Sathitkarnmanee, E.; Luvira, V.; Kamsa-Ard, S. Long-term outcome of surgical resection for intraductal papillary neoplasm of the bile duct. J. Gastroenterol. Hepatol. 2017, 32, 527–533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luvira, V.; Somsap, K.; Pugkhem, A.; Eurboonyanun, C.; Luvira, V.; Bhudhisawasdi, V.; Pairojkul, C.; Kamsa Ard, S. Morphological classification of intraductal papillary neoplasm of the bile duct with survival correlation. Asian Pac. J. Cancer Prev. 2017, 18, 207–213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tejaswi, S.; Olson, K.A.; Loehfelm, T.W. Cholangioscopy in primary sclerosing cholangitis: A case series of dominant strictures and cholangiocarcinoma. VideoGIE 2021, 6, 277–281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Kakuda, Y.; Uesaka, K.; Miyata, T.; Yamamoto, Y.; Fukumura, Y.; Sato, Y.; Sasaki, M.; Harada, K.; Takase, M. Characterization of intraductal papillary neoplasm of bile duct with respect to histopathologic similarities to pancreatic intraductal papillary mucinous neoplasm. Hum. Pathol. 2016, 51, 103–113. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jung, G.; Park, K.M.; Lee, S.S.; Yu, E.; Hong, S.M.; Kim, J. Long-term clinical outcome of the surgically resected intraductal papillary neoplasm of the bile duct. J. Hepatol. 2012, 57, 787–793. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shin, H.R.; Oh, J.K.; Lim, M.K.; Shin, A.; Kong, H.J.; Jung, K.W.; Won, Y.J.; Park, S.; Park, S.J.; Hong, S.T. Descriptive epidemiology of cholangiocarcinoma and clonorchiasis in Korea. J. Korean Med. Sci. 2010, 25, 1011–1016. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muraki, T.; Reid, M.D.; Pehlivanoglu, B.; Gonzalez, R.S.; Sekhar, A.; Memis, B.; Xue, Y.; Cheng, J.; Jang, K.T.; Mittal, P.; et al. Variant anatomy of the biliary system as a cause of pancreatic and peri-ampullary cancers. HPB 2020, 22, 1675–1685. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aydin Mericöz, C.; Hacihasanoglu, E.; Muraki, T.; Pehlivanoglu, B.; Memis, B.; Mittal, P.; Polito, H.; Saka, B.; Everett, R.; Sarmiento, J.; et al. Evaluation and pathologic classification of choledochal cysts: Clinicopathologic analysis of 84 cases from the West. Am. J. Surg. Pathol. 2021, 45, 627–637. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abraham, S.C.; Lee, J.H.; Boitnott, J.K.; Argani, P.; Furth, E.E.; Wu, T.T. Microsatellite instability in intraductal papillary neoplasms of the biliary tract. Mod. Pathol. 2002, 15, 1309–1317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goeppert, B.; Stichel, D.; Toth, R.; Fritzsche, S.; Loeffler, M.A.; Schlitter, A.M.; Neumann, O.; Assenov, Y.; Vogel, M.N.; Mehrabi, A.; et al. Integrative analysis reveals early and distinct genetic and epigenetic changes in intraductal papillary and tubulopapillary cholangiocarcinogenesis. Gut 2022, 71, 391–401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsai, J.H.; Liau, J.Y.; Yuan, C.T.; Cheng, M.L.; Yuan, R.H.; Jeng, Y.M. RNF43 mutation frequently occurs with GNAS mutation and mucin hypersecretion in intraductal papillary neoplasms of the bile duct. Histopathology 2017, 70, 756–765. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sasaki, M.; Matsubara, T.; Nitta, T.; Sato, Y.; Nakanuma, Y. GNAS and KRAS mutations are common in intraductal papillary neoplasms of the bile duct. PLoS ONE 2013, 8, e81706. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsai, J.H.; Yuan, R.H.; Chen, Y.L.; Liau, J.Y.; Jeng, Y.M. GNAS is frequently mutated in a specific subgroup of intraductal papillary neoplasms of the bile duct. Am. J. Surg. Pathol. 2013, 37, 1862–1870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, H.; Lim, J.H.; Jang, K.T.; Kim, M.J.; Lee, J.; Lee, J.Y.; Choi, D.; Lim, H.K.; Choi, D.W.; Lee, J.K.; et al. Morphology of intraductal papillary neoplasm of the bile ducts: Radiologic-pathologic correlation. Abdom. Imaging 2011, 36, 438–446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shibahara, H.; Tamada, S.; Goto, M.; Oda, K.; Nagino, M.; Nagasaka, T.; Batra, S.K.; Hollingsworth, M.A.; Imai, K.; Nimura, Y.; et al. Pathologic features of mucin-producing bile duct tumors: Two histopathologic categories as counterparts of pancreatic intraductal papillary-mucinous neoplasms. Am. J. Surg. Pathol. 2004, 28, 327–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y.; Fujii, T.; Itatsu, K.; Nakamura, K.; Minato, H.; Kasashima, S.; Kurumaya, H.; Katayanagi, K.; Kawashima, A.; Masuda, S.; et al. Biliary papillary tumors share pathological features with intraductal papillary mucinous neoplasm of the pancreas. Hepatology 2006, 44, 1333–1343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, K.M.; Lee, J.K.; Shin, J.U.; Lee, K.H.; Lee, K.T.; Sung, J.Y.; Jang, K.T.; Heo, J.S.; Choi, S.H.; Choi, D.W.; et al. Clinicopathologic features of intraductal papillary neoplasm of the bile duct according to histologic subtype. Am. J. Gastroenterol. 2012, 107, 118–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fukumura, Y.; Nakanuma, Y.; Kakuda, Y.; Takase, M.; Yao, T. Clinicopathological features of intraductal papillary neoplasms of the bile duct: A comparison with intraductal papillary mucinous neoplasm of the pancreas with reference to subtypes. Virchows Arch. 2017, 471, 65–76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kubota, K.; Jang, J.Y.; Nakanuma, Y.; Jang, K.T.; Haruyama, Y.; Fukushima, N.; Furukawa, T.; Hong, S.M.; Sakuraoka, Y.; Kim, H.; et al. Clinicopathological characteristics of intraductal papillary neoplasm of the bile duct: A Japan-Korea collaborative study. J. Hepatobiliary Pancreat. Sci. 2020, 27, 581–597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Uesaka, K.; Okamura, Y.; Terada, T.; Fukumura, Y.; Kakuda, Y.; Sugino, T.; Sato, Y.; Taek, J.K.; Park, Y.N. Reappraisal of pathological features of intraductal papillary neoplasm of bile duct with respect to the type 1 and 2 subclassifications. Hum. Pathol. 2021, 111, 21–35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Uchida, T.; Sato, Y.; Uesaka, K. An S100P-positive biliary epithelial field is a preinvasive intraepithelial neoplasm in nodular-sclerosing cholangiocarcinoma. Hum. Pathol. 2017, 60, 46–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schlitter, A.M.; Jang, K.T.; Klöppel, G.; Saka, B.; Hong, S.M.; Choi, H.; Offerhaus, G.J.; Hruban, R.H.; Zen, Y.; Konukiewitz, B.; et al. Intraductal tubulopapillary neoplasms of the bile ducts: Clinicopathologic, immunohistochemical, and molecular analysis of 20 cases. Mod. Pathol. 2015, 28, 1249–1264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamao, T.; Hayashi, H.; Higashi, T.; Takeyama, H.; Kaida, T.; Nitta, H.; Hashimoto, D.; Chikamoto, A.; Beppu, T.; Baba, H. Colon cancer metastasis mimicking intraductal papillary neoplasm of the extra-hepatic bile duct. Int. J. Surg. Case Rep. 2015, 10, 91–93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katabi, N.; Torres, J.; Klimstra, D.S. Intraductal tubular neoplasms of the bile ducts. Am. J. Surg. Pathol. 2012, 36, 1647–1655. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y.; Amarapurkar, A.D.; Portmann, B.C. Intraductal tubulopapillary neoplasm of the bile duct: Potential origin from peribiliary cysts. Hum. Pathol. 2012, 43, 440–445. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, H.J.; Jang, K.T.; Heo, J.S.; Choi, Y.L.; Han, J.; Kim, S.H. A potential case of intraductal tubulopapillary neoplasms of the bile duct. Pathol. Int. 2010, 60, 630–635. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akita, M.; Hong, S.M.; Sung, Y.N.; Kim, M.J.; Ajiki, T.; Fukumoto, T.; Itoh, T.; Zen, Y. Biliary intraductal tubule-forming neoplasm: A whole exome sequencing study of MUC5AC-positive and -negative cases. Histopathology 2020, 76, 1005–1012. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gross, C.; Engleitner, T.; Lange, S.; Weber, J.; Jesinghaus, M.; Konukiewitz, B.; Muckenhuber, A.; Steiger, K.; Pfarr, N.; Goeppert, B.; et al. Whole exome sequencing of biliary tubulopapillary neoplasms reveals common mutations in chromatin remodeling genes. Cancers 2021, 13, 2742. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pehlivanoglu, B.; Adsay, V. Intraductal tubulopapillary neoplasms of the bile ducts: Identity, clinicopathologic characteristics, and differential diagnosis of a distinct entity among intraductal tumors. Hum. Pathol. 2023, 132, 12–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Innocenti, L.; Rotondo, M.I.; Donati, F.; Boggi, U.; Campani, D. Intraductal oncocytic papillary neoplasm (IOPN): Two case reports and review of the literature. Transl. Cancer Res. 2023, 12, 663–672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanuma, Y.; Sato, Y.; Kakuda, Y.; Naito, Y.; Fukumura, Y.; Fukushima, M.; Minato, H.; Aishima, S.; Ohike, N.; Furukawa, T. Interobserver agreement of pathologic classification and grading of tumoral intraductal pre-invasive neoplasms of the bile duct. Ann. Diagn. Pathol. 2024, 69, 152247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chun, J.; Sung, Y.N.; An, S.; Hong, S.M. Oncocytic type has distinct immunohistochemical and recurrence-free survival than other histologic types of the intraductal papillary neoplasm of the bile duct. Hum. Pathol. 2024, 148, 72–80. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanaka, M.; Fukushima, N.; Noda, N.; Shibahara, J.; Kokudo, N.; Fukayama, M. Intraductal oncocytic papillary neoplasm of the bile duct: Clinicopathologic and immunohistochemical characteristics of 6 cases. Hum. Pathol. 2009, 40, 1543–1552. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liszka, L.; Pajak, J.; Zielińska-Pajak, E.; Krzych, L.; Gołka, D.; Mrowiec, S.; Lampe, P. Intraductal oncocytic papillary neoplasms of the pancreas and bile ducts: A description of five new cases and review based on a systematic survey of the literature. J. Hepatobiliary Pancreat. Sci. 2010, 17, 246–261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zen, Y.; Fujii, T.; Itatsu, K.; Nakamura, K.; Konishi, F.; Masuda, S.; Mitsui, T.; Asada, Y.; Miura, S.; Miyayama, S.; et al. Biliary cystic tumors with bile duct communication: A cystic variant of intraductal papillary neoplasm of the bile duct. Mod. Pathol. 2006, 19, 1243–1254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basturk, O.; Chung, S.M.; Hruban, R.H.; Adsay, N.V.; Askan, G.; Iacobuzio-Donahue, C.; Balci, S.; Zee, S.Y.; Memis, B.; Shia, J.; et al. Distinct pathways of pathogenesis of intraductal oncocytic papillary neoplasms and intraductal papillary mucinous neoplasms of the pancreas. Virchows Arch. 2016, 469, 523–532. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basturk, O.; Tan, M.; Bhanot, U.; Allen, P.; Adsay, V.; Scott, S.N.; Shah, R.; Berger, M.F.; Askan, G.; Dikoglu, E.; et al. The oncocytic subtype is genetically distinct from other pancreatic intraductal papillary mucinous neoplasm subtypes. Mod. Pathol. 2016, 29, 1058–1069. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Paolino, G.; Basturk, O.; Esposito, I.; Hong, S.M.; Brosens, L.A.; Tarcan, Z.; Wood, L.D.; Gkountakos, A.; Omori, Y.; Mattiolo, P.; et al. Comprehensive characterization of intraductal oncocytic papillary neoplasm of the pancreas: A systematic and critical review. Mod. Pathol. 2024, 37, 100554. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singhi, A.D.; Wood, L.D.; Parks, E.; Torbenson, M.S.; Felsenstein, M.; Hruban, R.H.; Nikiforova, M.N.; Wald, A.I.; Kaya, C.; Nikiforov, Y.E.; et al. Recurrent rearrangements in PRKACA and PRKACB in intraductal oncocytic papillary neoplasms of the pancreas and bile duct. Gastroenterology 2020, 158, 573–582.e2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Itoh, T.; Omori, Y.; Seino, M.; Hirose, K.; Date, F.; Ono, Y.; Mizukami, Y.; Aoki, S.; Ishida, M.; Mizuma, M.; et al. Gene rearrangement and expression of PRKACA and PRKACB govern morphobiology of pancreatobiliary oncocytic neoplasms. Mod. Pathol. 2024, 37, 100358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vyas, M.; Hechtman, J.F.; Zhang, Y.; Benayed, R.; Yavas, A.; Askan, G.; Shia, J.; Klimstra, D.S.; Basturk, O. DNAJB1-PRKACA fusions occur in oncocytic pancreatic and biliary neoplasms and are not specific for fibrolamellar hepatocellular carcinoma. Mod. Pathol. 2020, 33, 648–656. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maimaitiaili, Y.; Fukumura, Y.; Hirabayashi, K.; Kinowaki, Y.; Naito, Y.; Saito, A.; Rong, L.; Nakahodo, J.; Yao, T. Investigation of PRKACA/-PRKACB fusion genes in oncocytic tumors of the pancreatobiliary and other systems. Virchows Arch. 2022, 481, 865–876. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adsay, N.V.; Adair, C.F.; Heffess, C.S.; Klimstra, D.S. Intraductal oncocytic papillary neoplasms of the pancreas. Am. J. Surg. Pathol. 1996, 20, 980–994. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.; Askan, G.; Adsay, V.; Allen, P.; Jarnagin, W.R.; Memis, B.; Sigel, C.; Seven, I.E.; Klimstra, D.S.; Basturk, O. Intraductal oncocytic papillary neoplasms: Clinical-pathologic characterization of 24 cases, with an emphasis on associated invasive carcinomas. Am. J. Surg. Pathol. 2019, 43, 656–661. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martin, R.C.; Klimstra, D.S.; Schwartz, L.; Yilmaz, A.; Blumgart, L.H.; Jarnagin, W. Hepatic intraductal oncocytic papillary carcinoma. Cancer 2002, 95, 2180–2187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanaka, M.; Takeshita, K.; Kunita, A.; Hasegawa, K.; Ushiku, T. PRKACA/PRKACB fusions in pancreatobiliary intraductal oncocytic papillary neoplasms including those with atypical morphology: An analysis of 22 cases expanding morphologic spectrum. Am. J. Surg. Pathol. 2024, 48, 1032–1040. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basturk, O.; Khayyata, S.; Klimstra, D.S.; Hruban, R.H.; Zamboni, G.; Coban, I.; Adsay, N.V. Preferential expression of MUC6 in oncocytic and pancreatobiliary types of intraductal papillary neoplasms highlights a pyloropancreatic pathway, distinct from the intestinal pathway, in pancreatic carcinogenesis. Am. J. Surg. Pathol. 2010, 34, 364–370. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Youn, J.M.; Hwang, S.; Ahn, C.S.; Moon, D.B.; Ha, T.Y.; Song, G.W.; Jung, D.H.; Hong, S.M. Clinicopathological features and long-term outcomes of intraductal papillary neoplasms of the bile duct of the liver: Single-institution experience with 146 patients. J. Gastrointest. Surg. 2022, 26, 1394–1405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xue, Y.; Reid, M.D.; Pehlivanoglu, B.; Obeng, R.C.; Jiang, H.; Memis, B.; Lui, S.K.; Sarmiento, J.; Kooby, D.; Maithel, S.K.; et al. Morphologic variants of pancreatic neuroendocrine tumors: Clinicopathologic analysis and prognostic stratification. Endocr. Pathol. 2020, 31, 239–253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mattiolo, P.; Scarpa, A.; Luchini, C. Hepatoid tumors of the gastrointestinal/pancreatobiliary district: Morphology, immunohistochemistry, and molecular profiles. Hum. Pathol. 2023, 132, 169–175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adsay, V.; Jang, K.T.; Roa, J.C.; Dursun, N.; Ohike, N.; Bagci, P.; Basturk, O.; Bandyopadhyay, S.; Cheng, J.D.; Sarmiento, J.M.; et al. Intracholecystic papillary-tubular neoplasms (ICPN) of the gallbladder (neoplastic polyps, adenomas, and papillary neoplasms that are ≥1.0 cm): Clinicopathologic and immunohistochemical analysis of 123 cases. Am. J. Surg. Pathol. 2012, 36, 1279–1301. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Albores-Saavedra, J.; Vardaman, C.J.; Vuitch, F. Non-neoplastic polypoid lesions and adenomas of the gallbladder. Pathol. Annu. 1993, 28, 145–177. [Google Scholar] [PubMed]
- Wistuba, I.I.; Miquel, J.F.; Gazdar, A.F.; Albores-Saavedra, J. Gallbladder adenomas have molecular abnormalities different from those present in gallbladder carcinomas. Hum. Pathol. 1999, 30, 21–25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Albores-Saavedra, J.; Chablé-Montero, F.; González-Romo, M.A.; Ramírez Jaramillo, M.; Henson, D.E. Adenomas of the gallbladder. Morphologic features, expression of gastric and intestinal mucins, and incidence of high-grade dysplasia/carcinoma in situ and invasive carcinoma. Hum. Pathol. 2012, 43, 1506–1513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muraki, T.; Pehlivanoglu, B.; Memis, B.; Reid, M.D.; Uehara, T.; Basturk, O.; Pernicka, J.G.; Klimstra, D.S.; Jarnagin, W.R.; Ito, T.; et al. Pancreatobiliary maljunction-associated gallbladder cancer is as common in the west, shows distinct clinicopathologic characteristics and offers an invaluable model for anatomy-induced reflux-associated physio-chemical carcinogenesis. Ann. Surg. 2022, 276, e32–e39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muraki, T.; Memis, B.; Reid, M.D.; Uehara, T.; Ito, T.; Hasebe, O.; Okaniwa, S.; Horigome, N.; Hisa, T.; Mittal, P.; et al. Reflux-associated cholecystopathy: Analysis of 76 gallbladders from patients with supra-Oddi union of the pancreatic duct and common bile duct (pancreatobiliary maljunction) elucidates a specific diagnostic pattern of mucosal hyperplasia as a prelude to carcinoma. Am. J. Surg. Pathol. 2017, 41, 1167–1177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, H.J.; Jee, C.D.; Kim, W.H. Mutation and altered expression of beta-catenin during gallbladder carcinogenesis. Am. J. Surg. Pathol. 2002, 26, 758–766. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yanagisawa, N.; Mikami, T.; Saegusa, M.; Okayasu, I. More frequent beta-catenin exon 3 mutations in gallbladder adenomas than in carcinomas indicate different lineages. Cancer Res. 2001, 61, 19–22. [Google Scholar] [PubMed]
- Pai, R.K.; Mojtahed, K.; Pai, R.K. Mutations in the RAS/RAF/MAP kinase pathway commonly occur in gallbladder adenomas but are uncommon in gallbladder adenocarcinomas. Appl. Immunohistochem. Mol. Morphol. 2011, 19, 133–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matthaei, H.; Wu, J.; Dal Molin, M.; Debeljak, M.; Lingohr, P.; Katabi, N.; Klimstra, D.S.; Adsay, N.V.; Eshleman, J.R.; Schulick, R.D.; et al. GNAS codon 201 mutations are uncommon in intraductal papillary neoplasms of the bile duct. HPB 2012, 14, 677–683. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fujisawa, M.; Matsushima, M.; Carreras, J.; Hirabayashi, K.; Kikuti, Y.Y.; Ueda, T.; Kaneko, M.; Fujimoto, R.; Sano, M.; Teramura, E.; et al. Whole-genome copy number and immunohistochemical analyses on surgically resected intracholecystic papillary neoplasms. Pathol. Int. 2021, 71, 823–830. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pehlivanoglu, B.; Balci, S.; Basturk, O.; Bagci, P.; Erbarut Seven, I.; Memis, B.; Dursun, N.; Jang, K.T.; Saka, B.; Ohike, N.; et al. Intracholecystic tubular non-mucinous neoplasm (ICTN) of the gallbladder: A clinicopathologically distinct, invasion-resistant entity. Virchows Arch. 2021, 478, 435–447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rowan, D.J.; Pehlivanoglu, B.; Memis, B.; Bagci, P.; Erbarut, I.; Dursun, N.; Jang, K.T.; Sarmiento, J.; Mucientes, F.; Cheng, J.D.; et al. Mural intracholecystic neoplasms arising in adenomyomatous nodules of the gallbladder: An analysis of 19 examples of a clinicopathologically distinct entity. Am. J. Surg. Pathol. 2020, 44, 1649–1657. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dursun, N.; Memis, B.; Pehlivanoglu, B.; Taskin, O.C.; Okcu, O.; Akkas, G.; Bagci, P.; Balci, S.; Saka, B.; Araya, J.C.; et al. Adenomyomas of the gallbladder: An analysis of frequency, clinicopathologic associations, and relationship to carcinoma of a malformative lesion. Arch. Pathol. Lab. Med. 2024, 148, 206–214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kozuka, S.; Tsubone, N.; Yasui, A.; Hachisuka, K. Relation of adenoma to carcinoma in the gallbladder. Cancer 1982, 50, 2226–2234. [Google Scholar] [CrossRef] [Scilit]
- Hoang, M.P.; Murakata, L.A.; Katabi, N.; Henson, D.E.; Albores-Saavedra, J. Invasive papillary carcinomas of the extrahepatic bile ducts: A clinicopathologic and immunohistochemical study of 13 cases. Mod. Pathol. 2002, 15, 1251–1258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sciarra, A.; Missiaglia, E.; Trimech, M.; Melloul, E.; Brouland, J.P.; Sempoux, C.; La Rosa, S. Gallbladder mixed neuroendocrine-non-neuroendocrine neoplasm (MINEN) arising in intracholecystic papillary neoplasm: Clinicopathologic and molecular analysis of a case and review of the literature. Endocr. Pathol. 2020, 31, 84–93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basturk, O.; Adsay, V.; Askan, G.; Dhall, D.; Zamboni, G.; Shimizu, M.; Cymes, K.; Carneiro, F.; Balci, S.; Sigel, C.; et al. Intraductal tubulopapillary neoplasm of the pancreas: A clinicopathologic and immunohistochemical analysis of 33 cases. Am. J. Surg. Pathol. 2017, 41, 313–325. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Charbel, A.; Tavernar, L.; Albrecht, T.; Brinkmann, F.; Verheij, J.; Roos, E.; Vogel, M.N.; Köhler, B.; Springfeld, C.; Brobeil, A.; et al. Spatiotemporal analysis of tumour-infiltrating immune cells in biliary carcinogenesis. Br. J. Cancer 2022, 127, 1603–1614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, N.; Li, J.; Gu, A.; Li, M.; Liu, Y. Single-cell multi-omics in biliary tract cancers: Decoding heterogeneity, microenvironment, and treatment strategies. Mol. Biomed. 2025, 6, 82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silva, R.S.D.; Schmitt, F. Next step of molecular pathology: Next-generation sequencing in cytology. J. Pathol. Transl. Med. 2024, 58, 291–298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Longerich, T.; Stenzinger, A.; Schirmacher, P. Molecular diagnostics of hepatobiliary and pancreatic neoplasias. Virchows Arch. 2024, 484, 263–272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoyer, D.P.; Ting, S.; Rogacka, N.; Koitka, S.; Hosch, R.; Flaschel, N.; Haubold, J.; Malamutmann, E.; Stüben, B.O.; Treckmann, J.; et al. AI-based digital histopathology for perihilar cholangiocarcinoma: A step, not a jump. J. Pathol. Inform. 2024, 15, 100345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pantelakos, S.; Nifora, M.; Agrogiannis, G. The automatable activity-based approach to complexity unit scoring as a task-specific model approach to monetizing outcomes of pathology artificial intelligence solutions. J. Pathol. Transl. Med. 2025, 59, 225–234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaktah, L.A.; Carrero, Z.I.; Hewitt, K.J.; Gustav, M.; Cecchini, M.; Foersch, S.; Berezowska, S.; Kather, J.N. Application of artificial intelligence and digital tools in cancer pathology. Lancet Digit. Health 2025, 7, 100933. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xiao, H.; Wang, J.; Weng, Z.; Lin, X.; Shu, M.; Shen, J.; Sun, P.; Cai, M.; Xiang, X.; Li, B.; et al. A histopathology-based artificial intelligence system assisting the screening of genetic alteration in intrahepatic cholangiocarcinoma. Br. J. Cancer 2025, 132, 195–202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
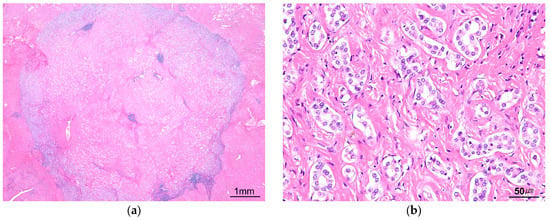
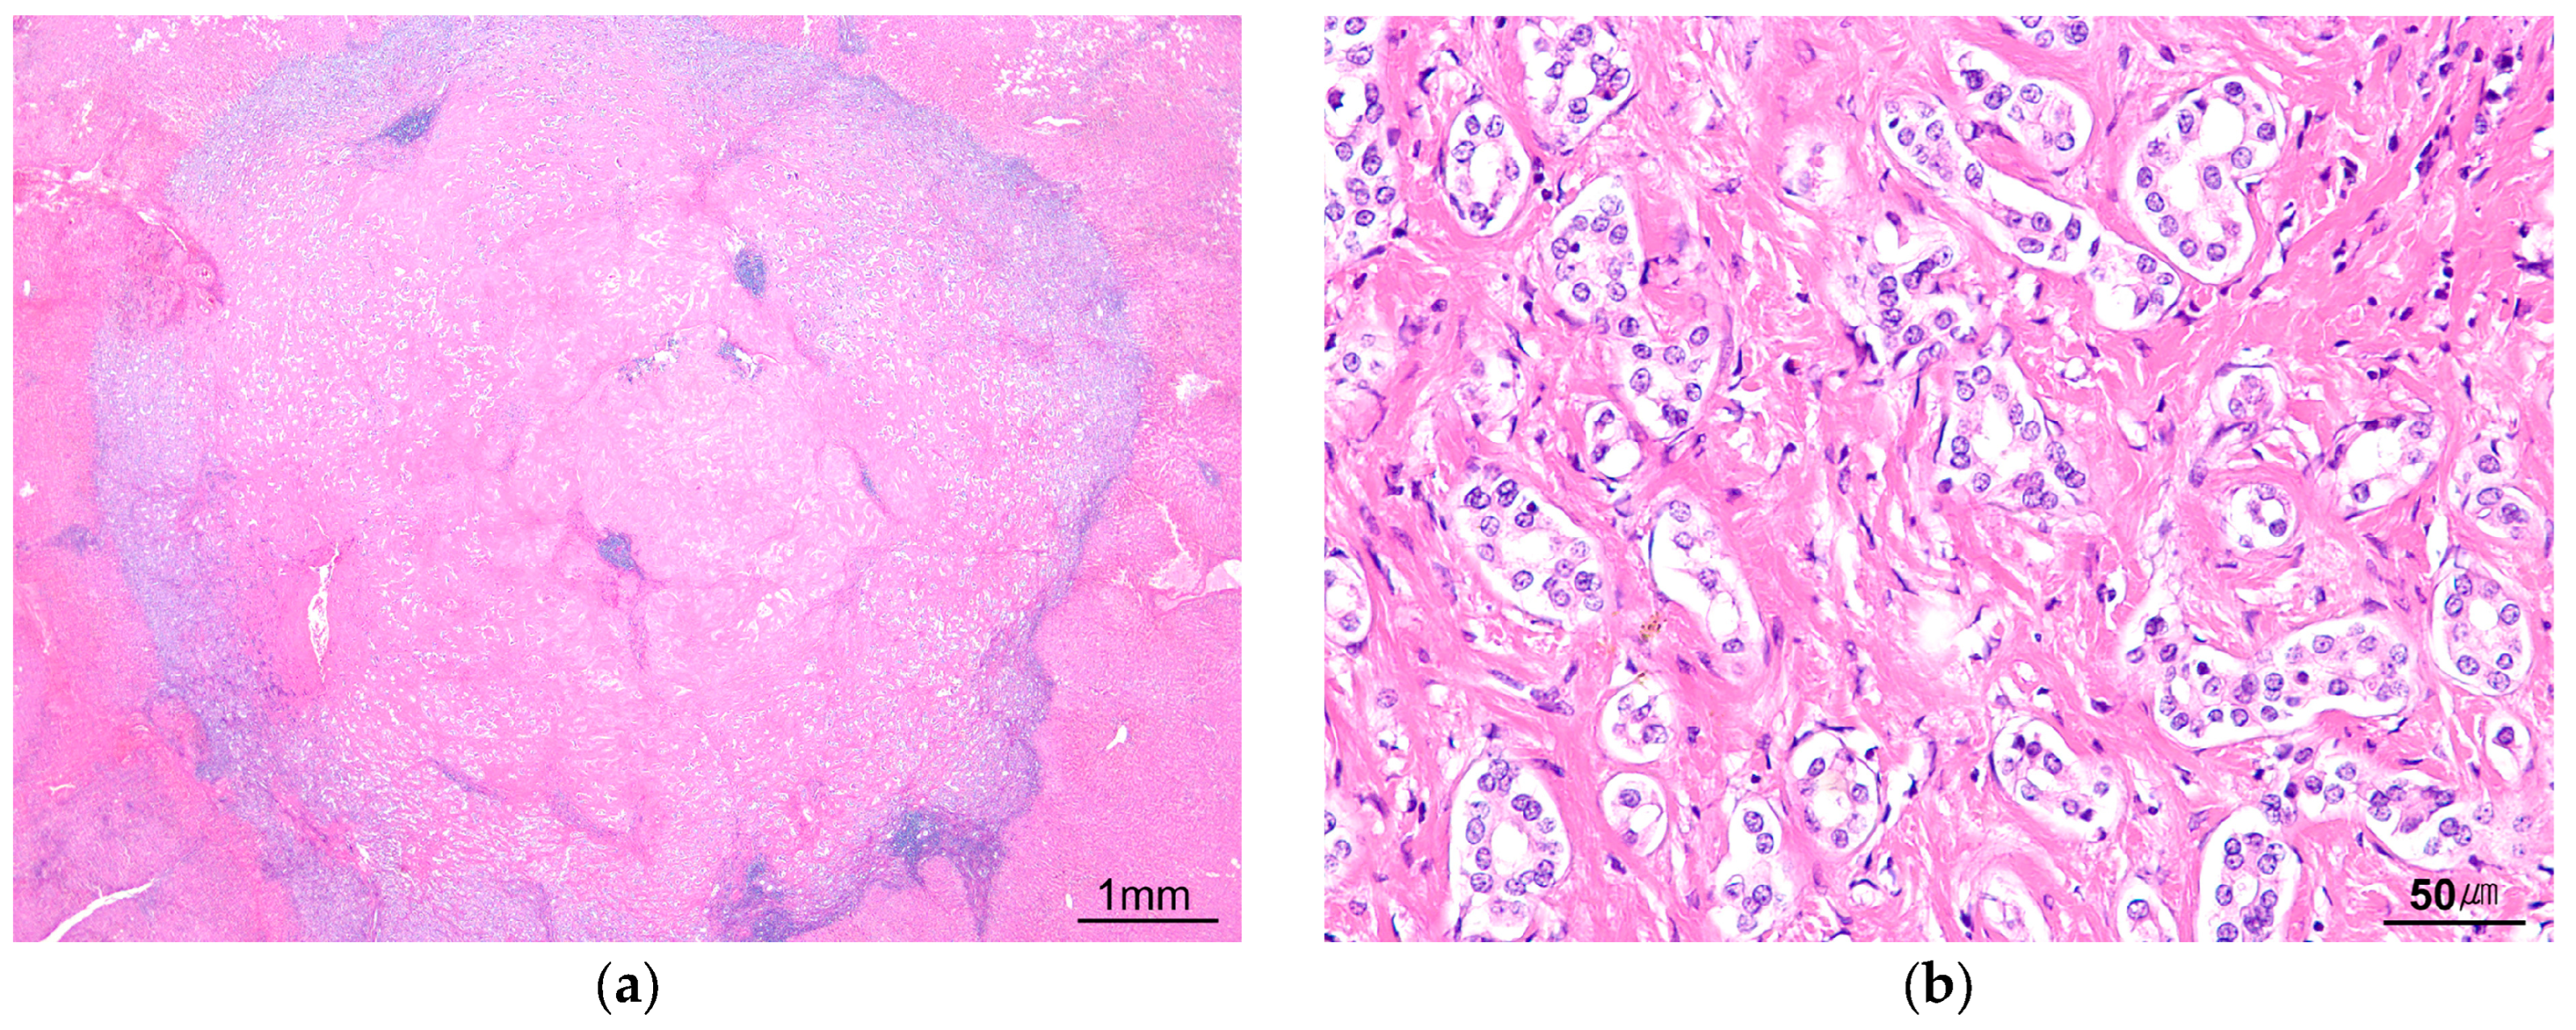
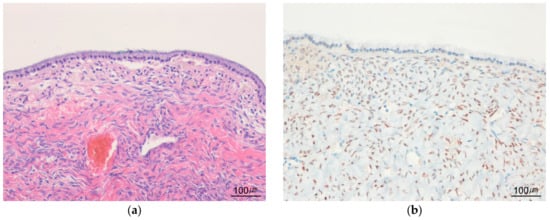
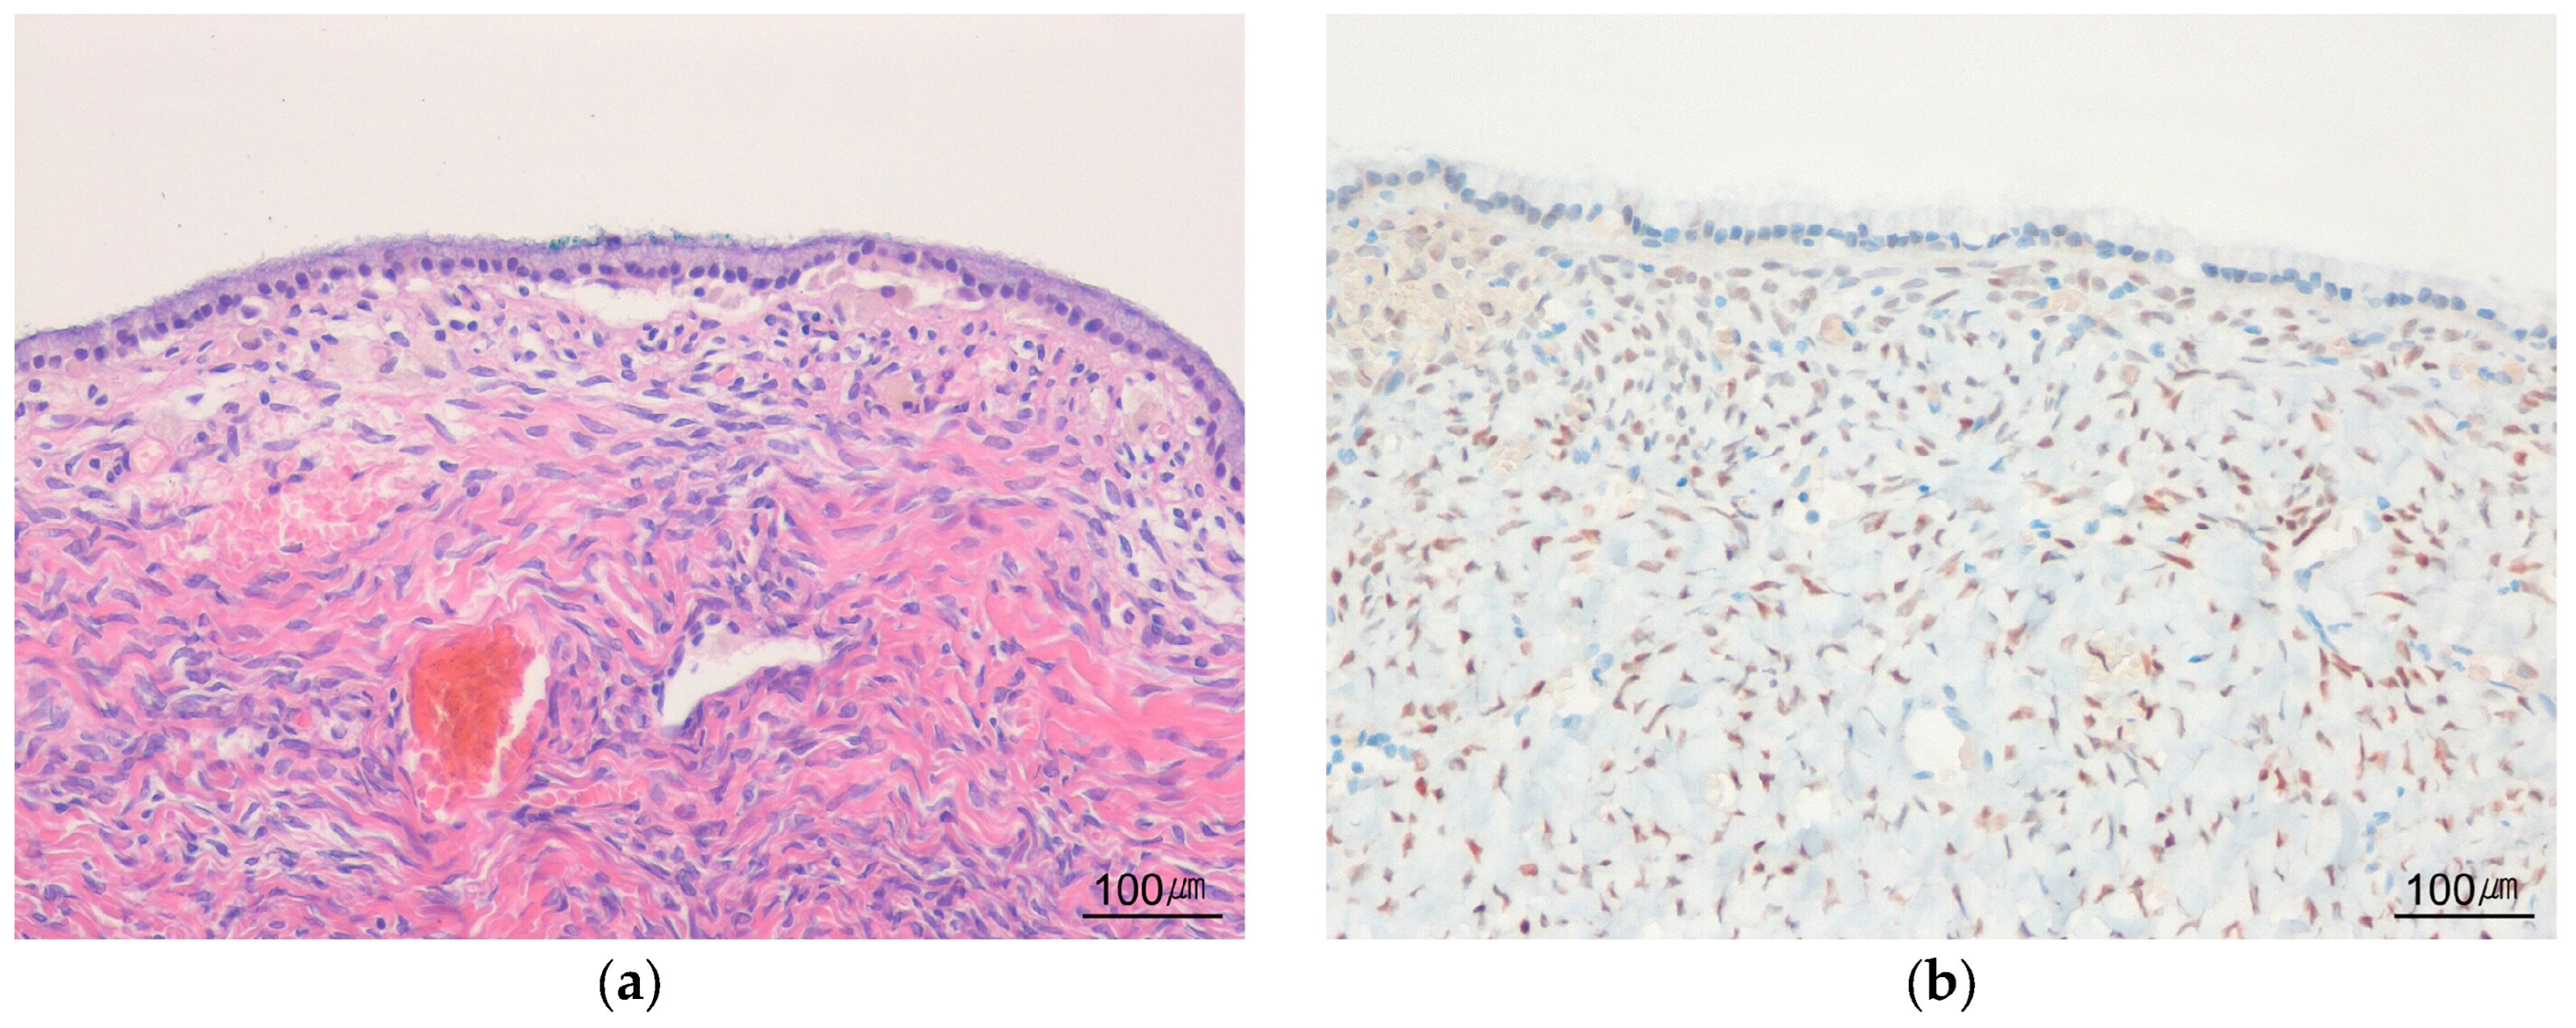
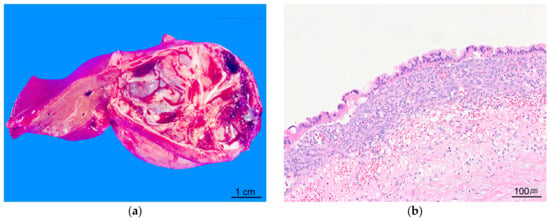
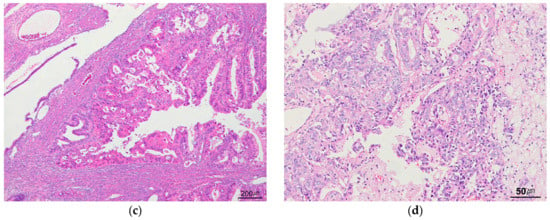
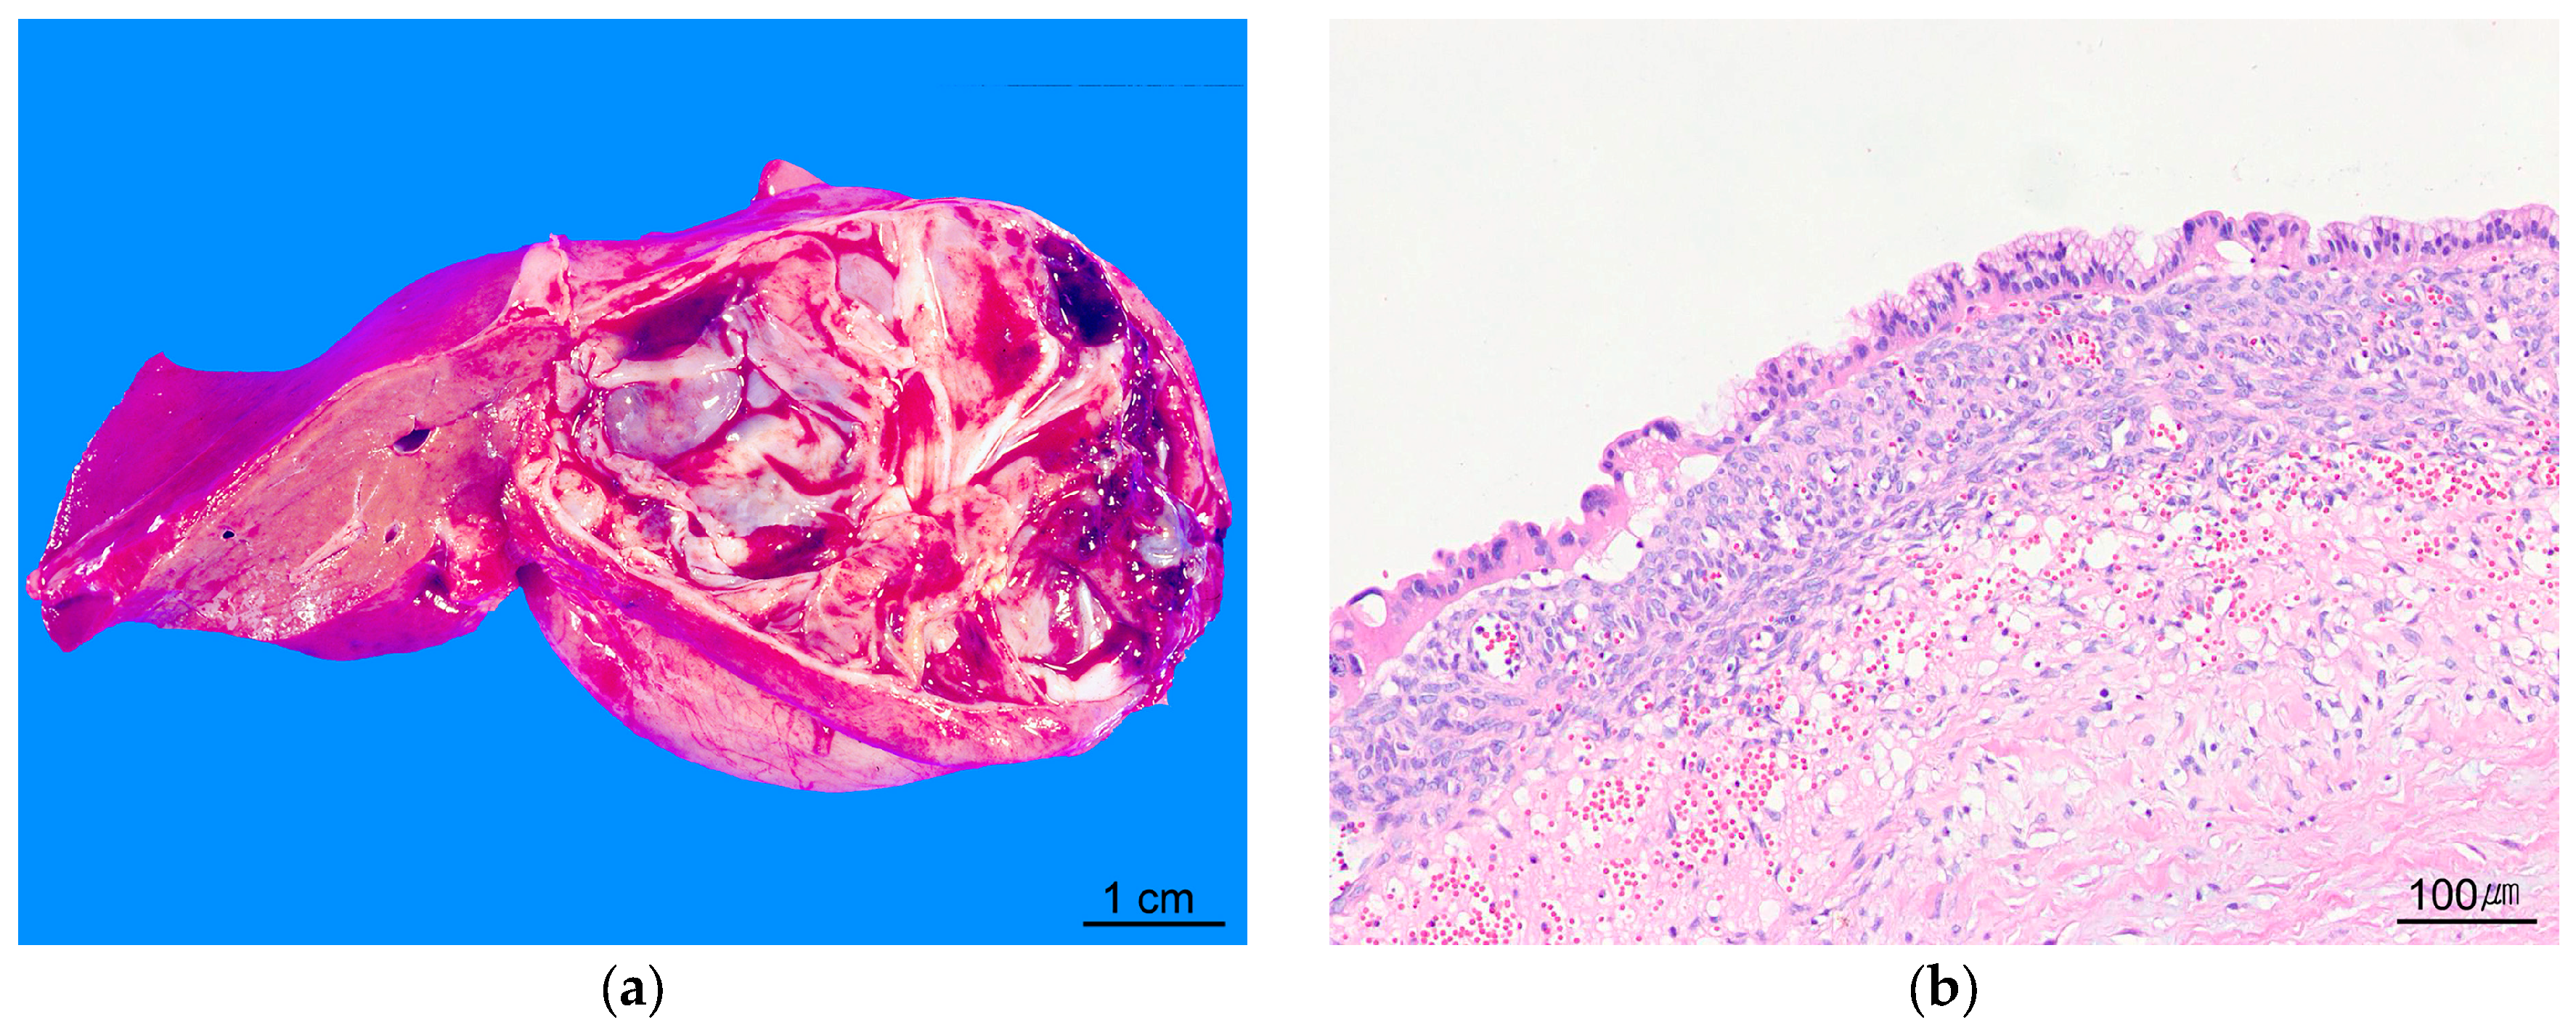
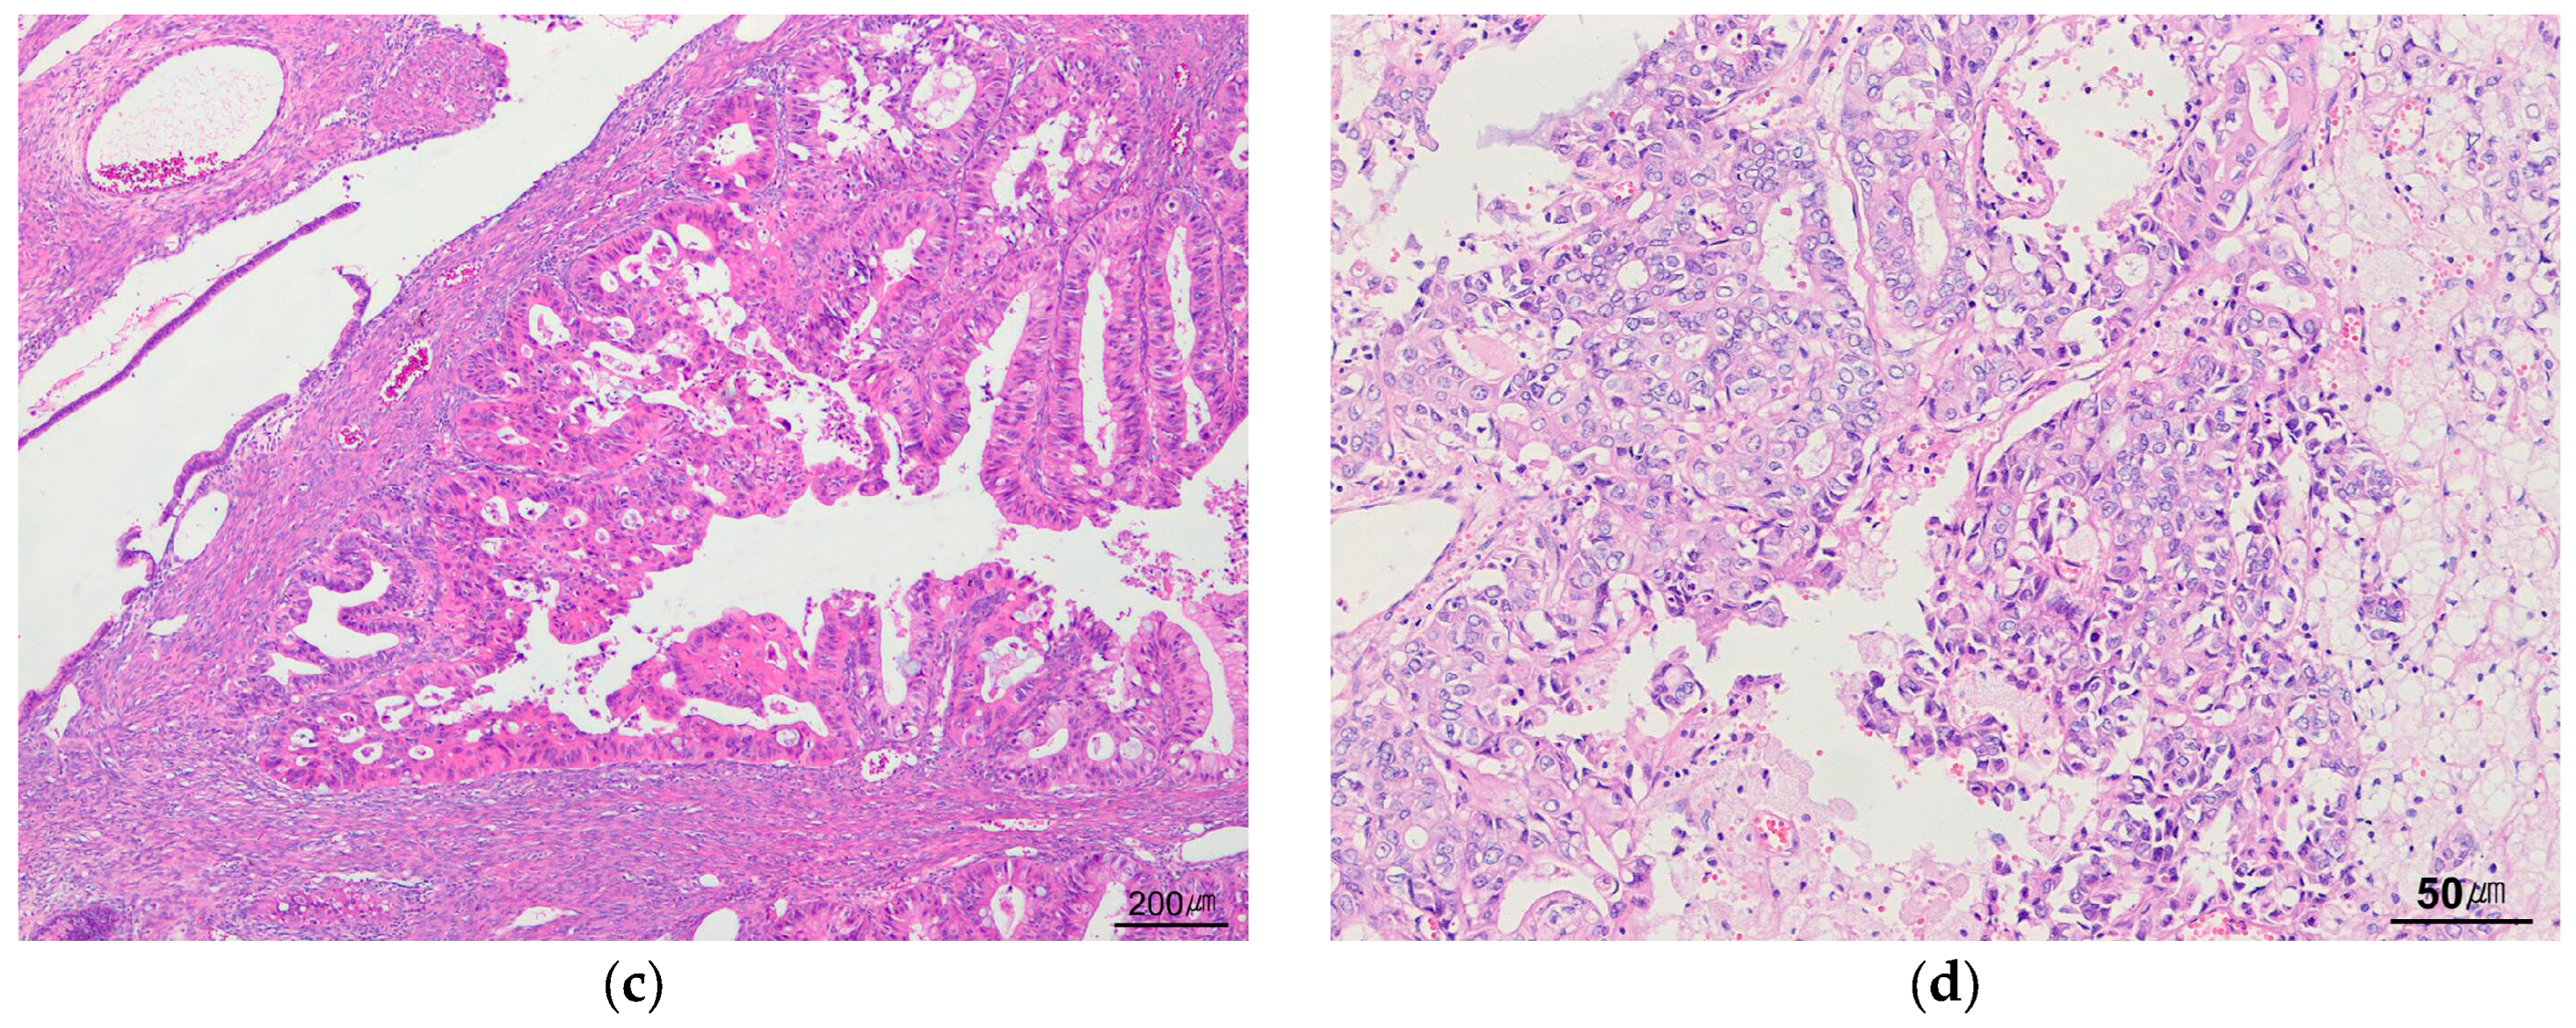
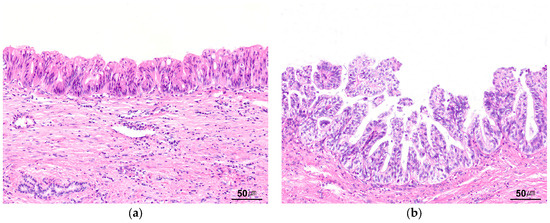
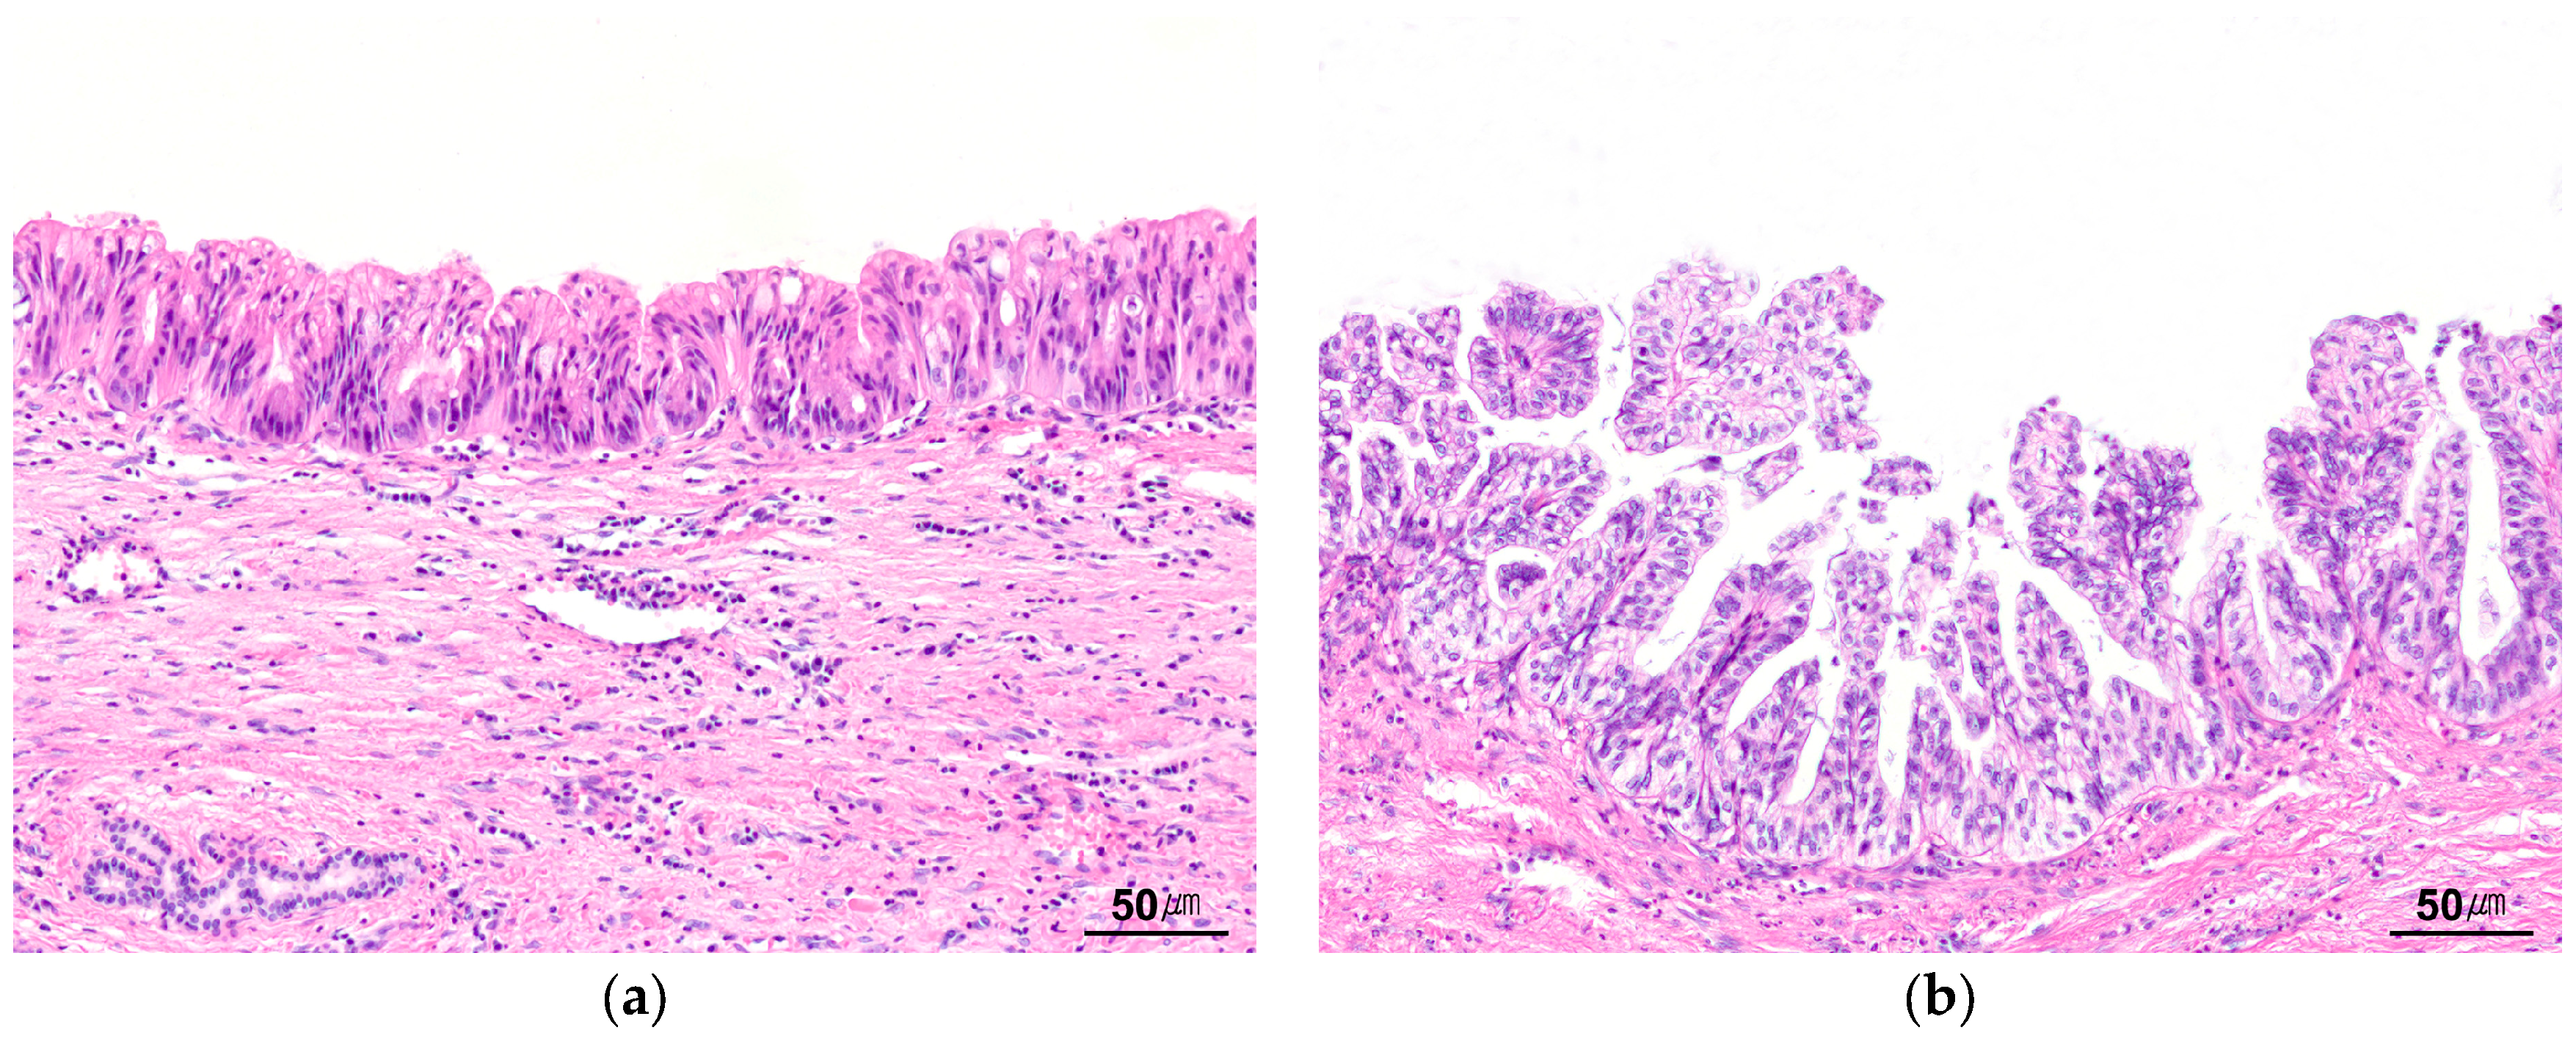
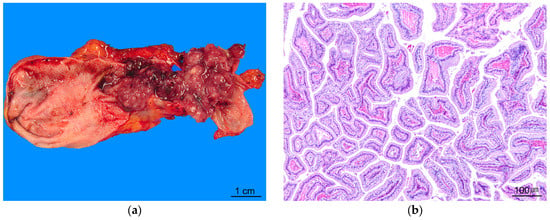
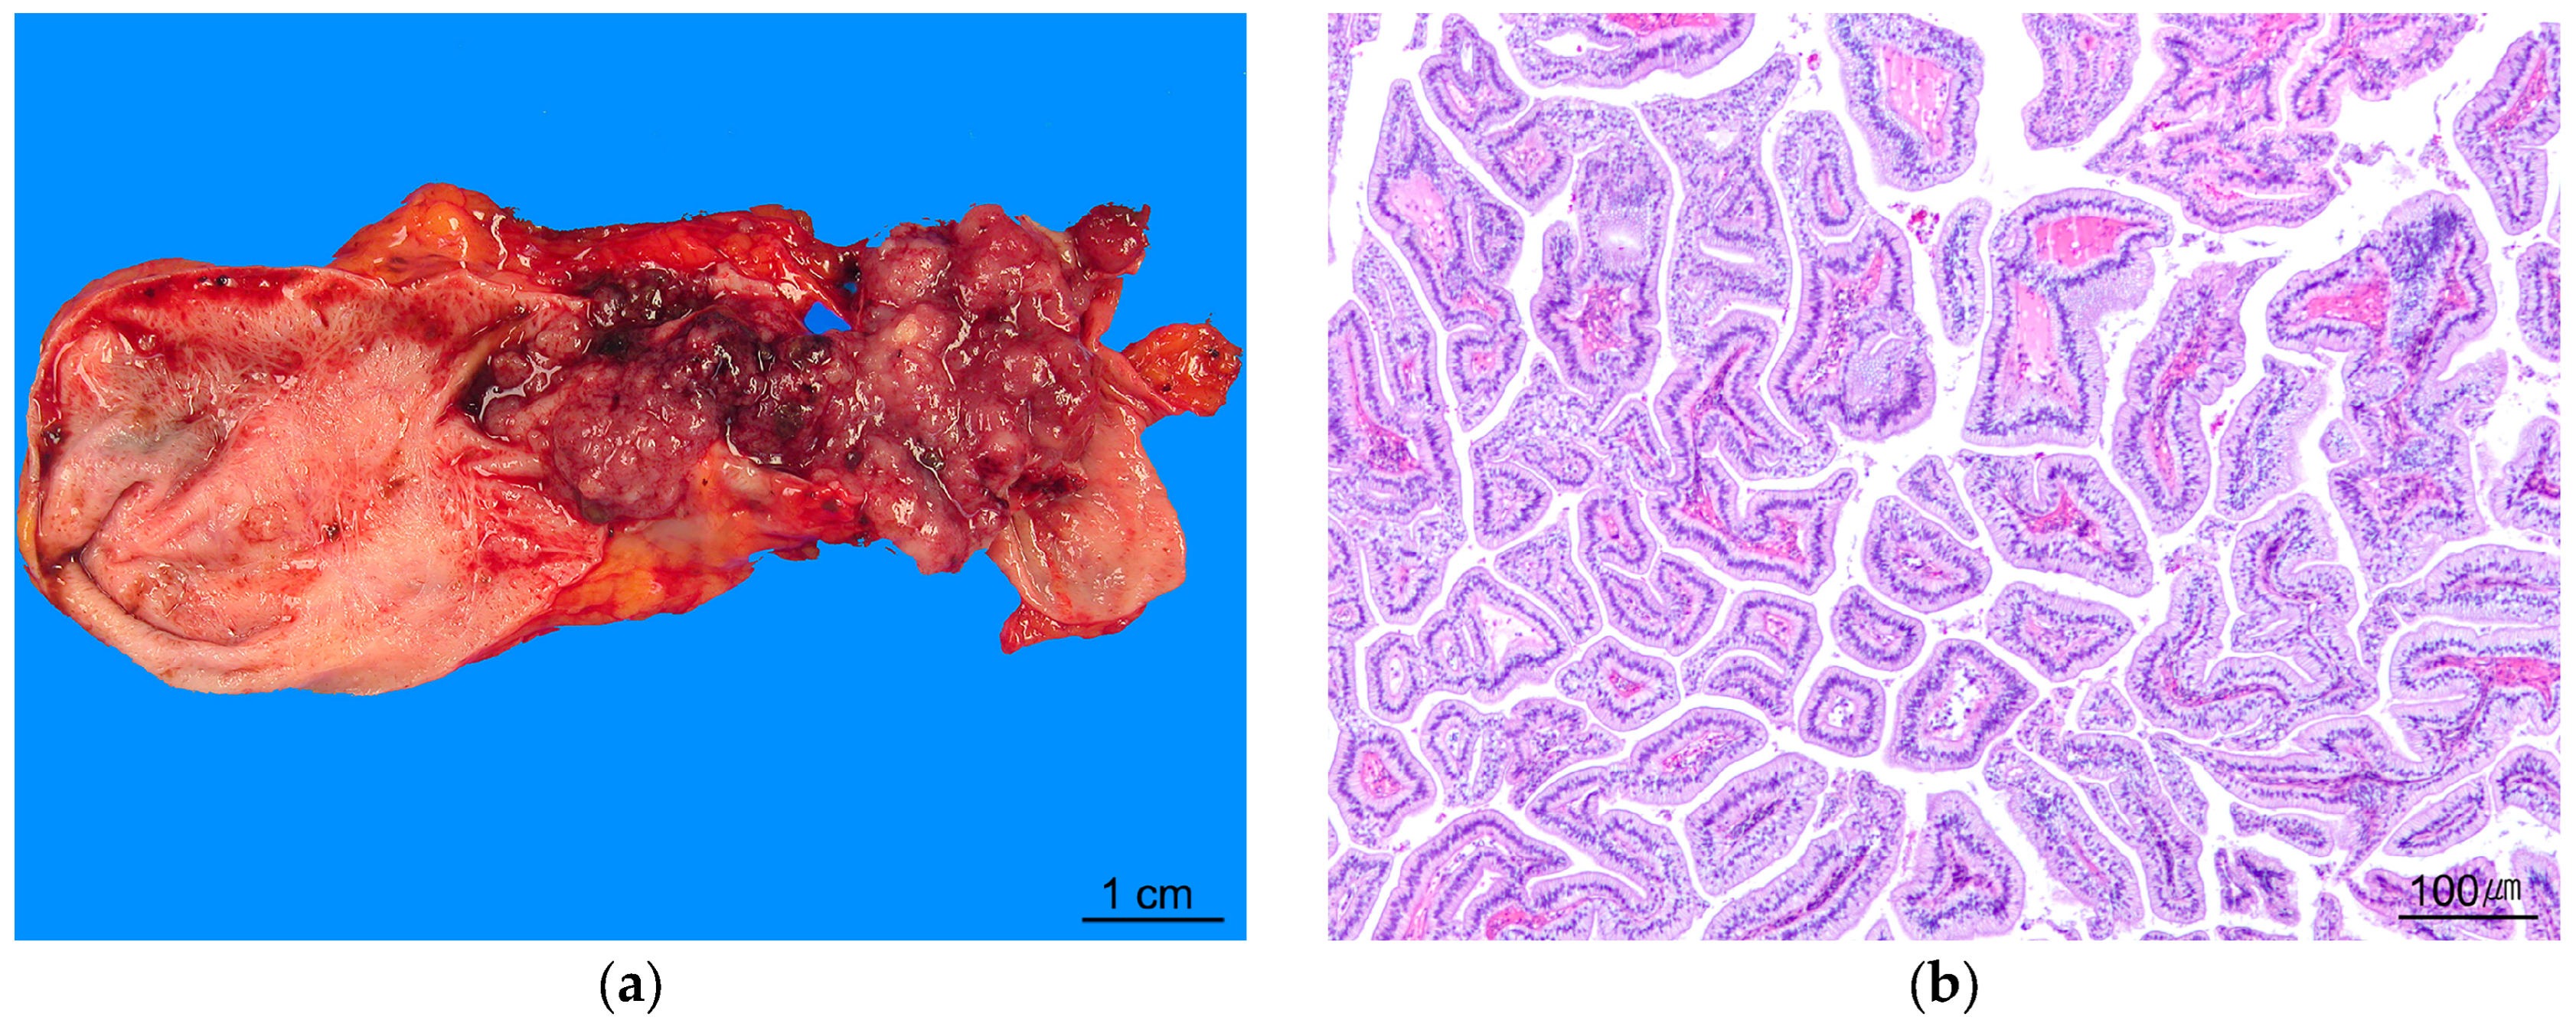
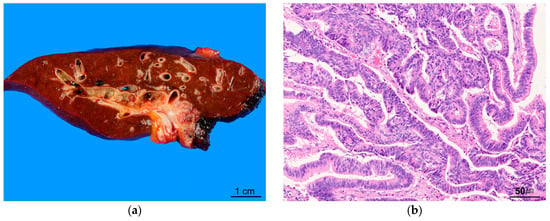
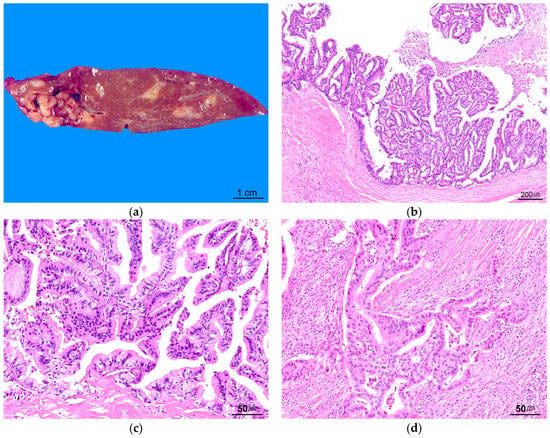
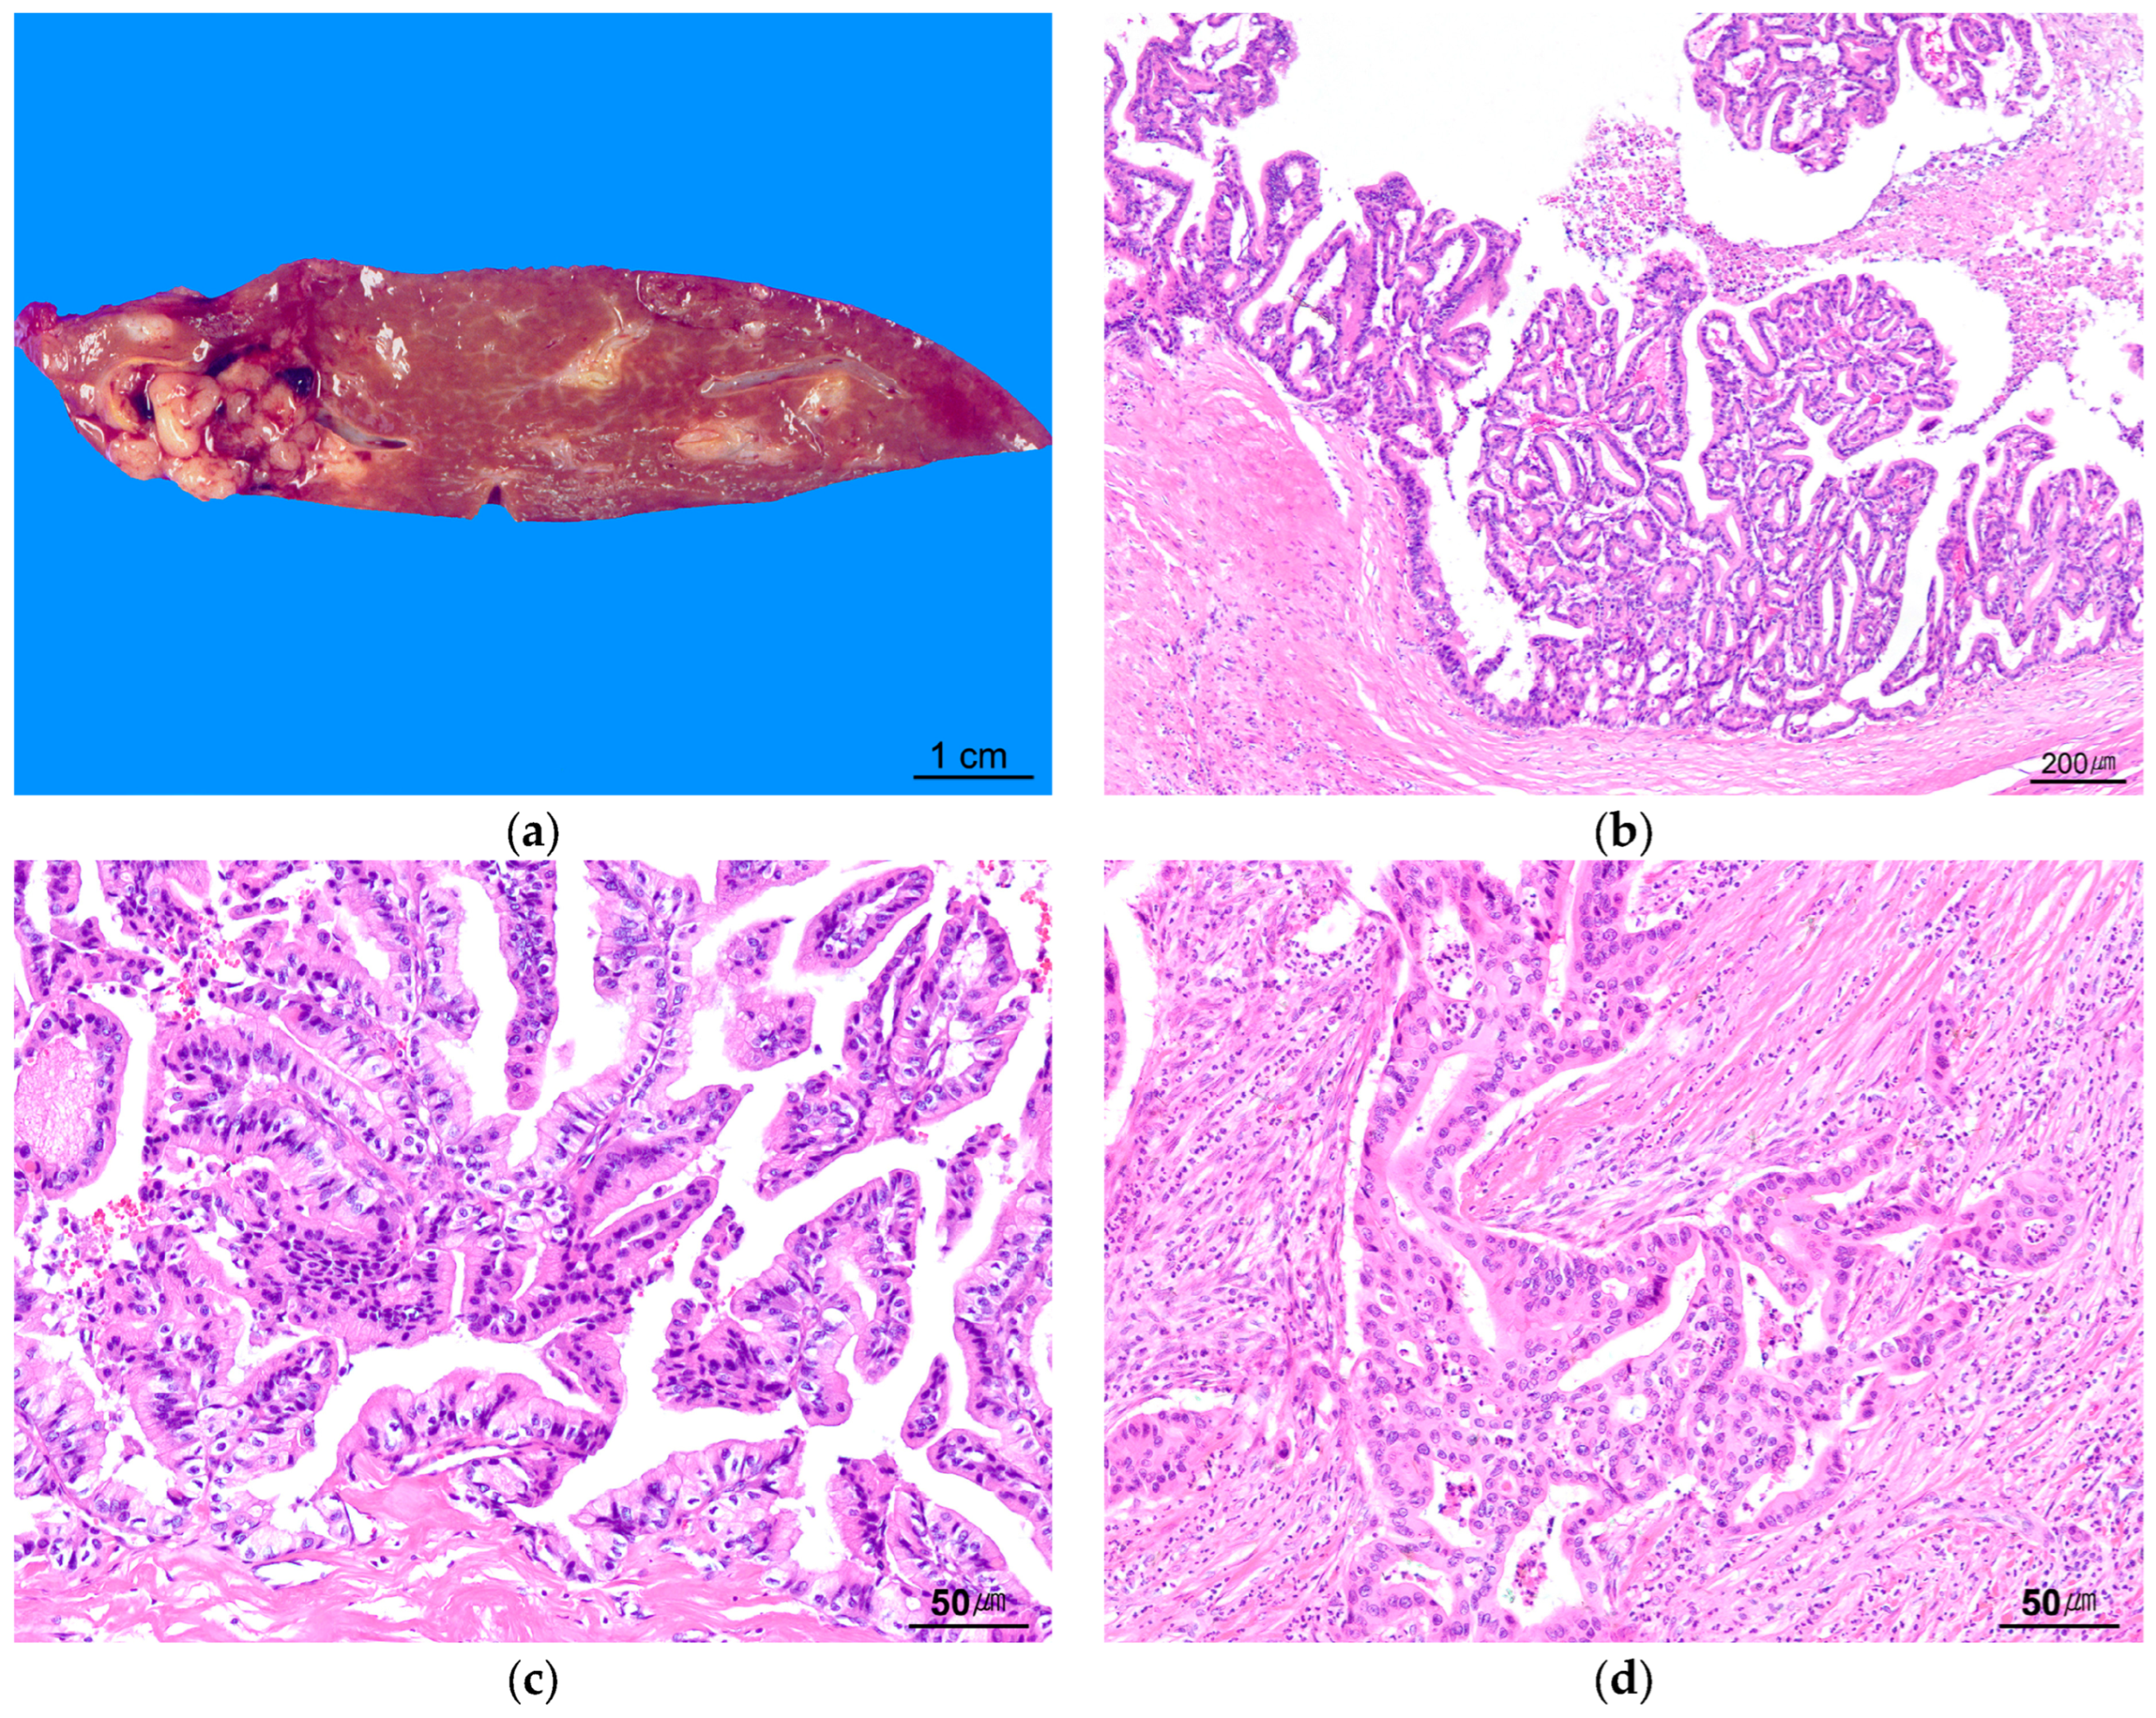
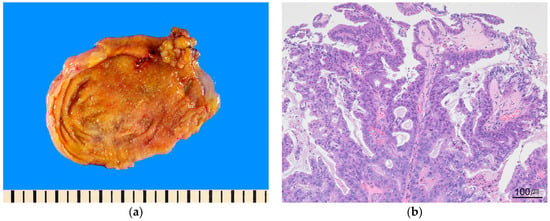
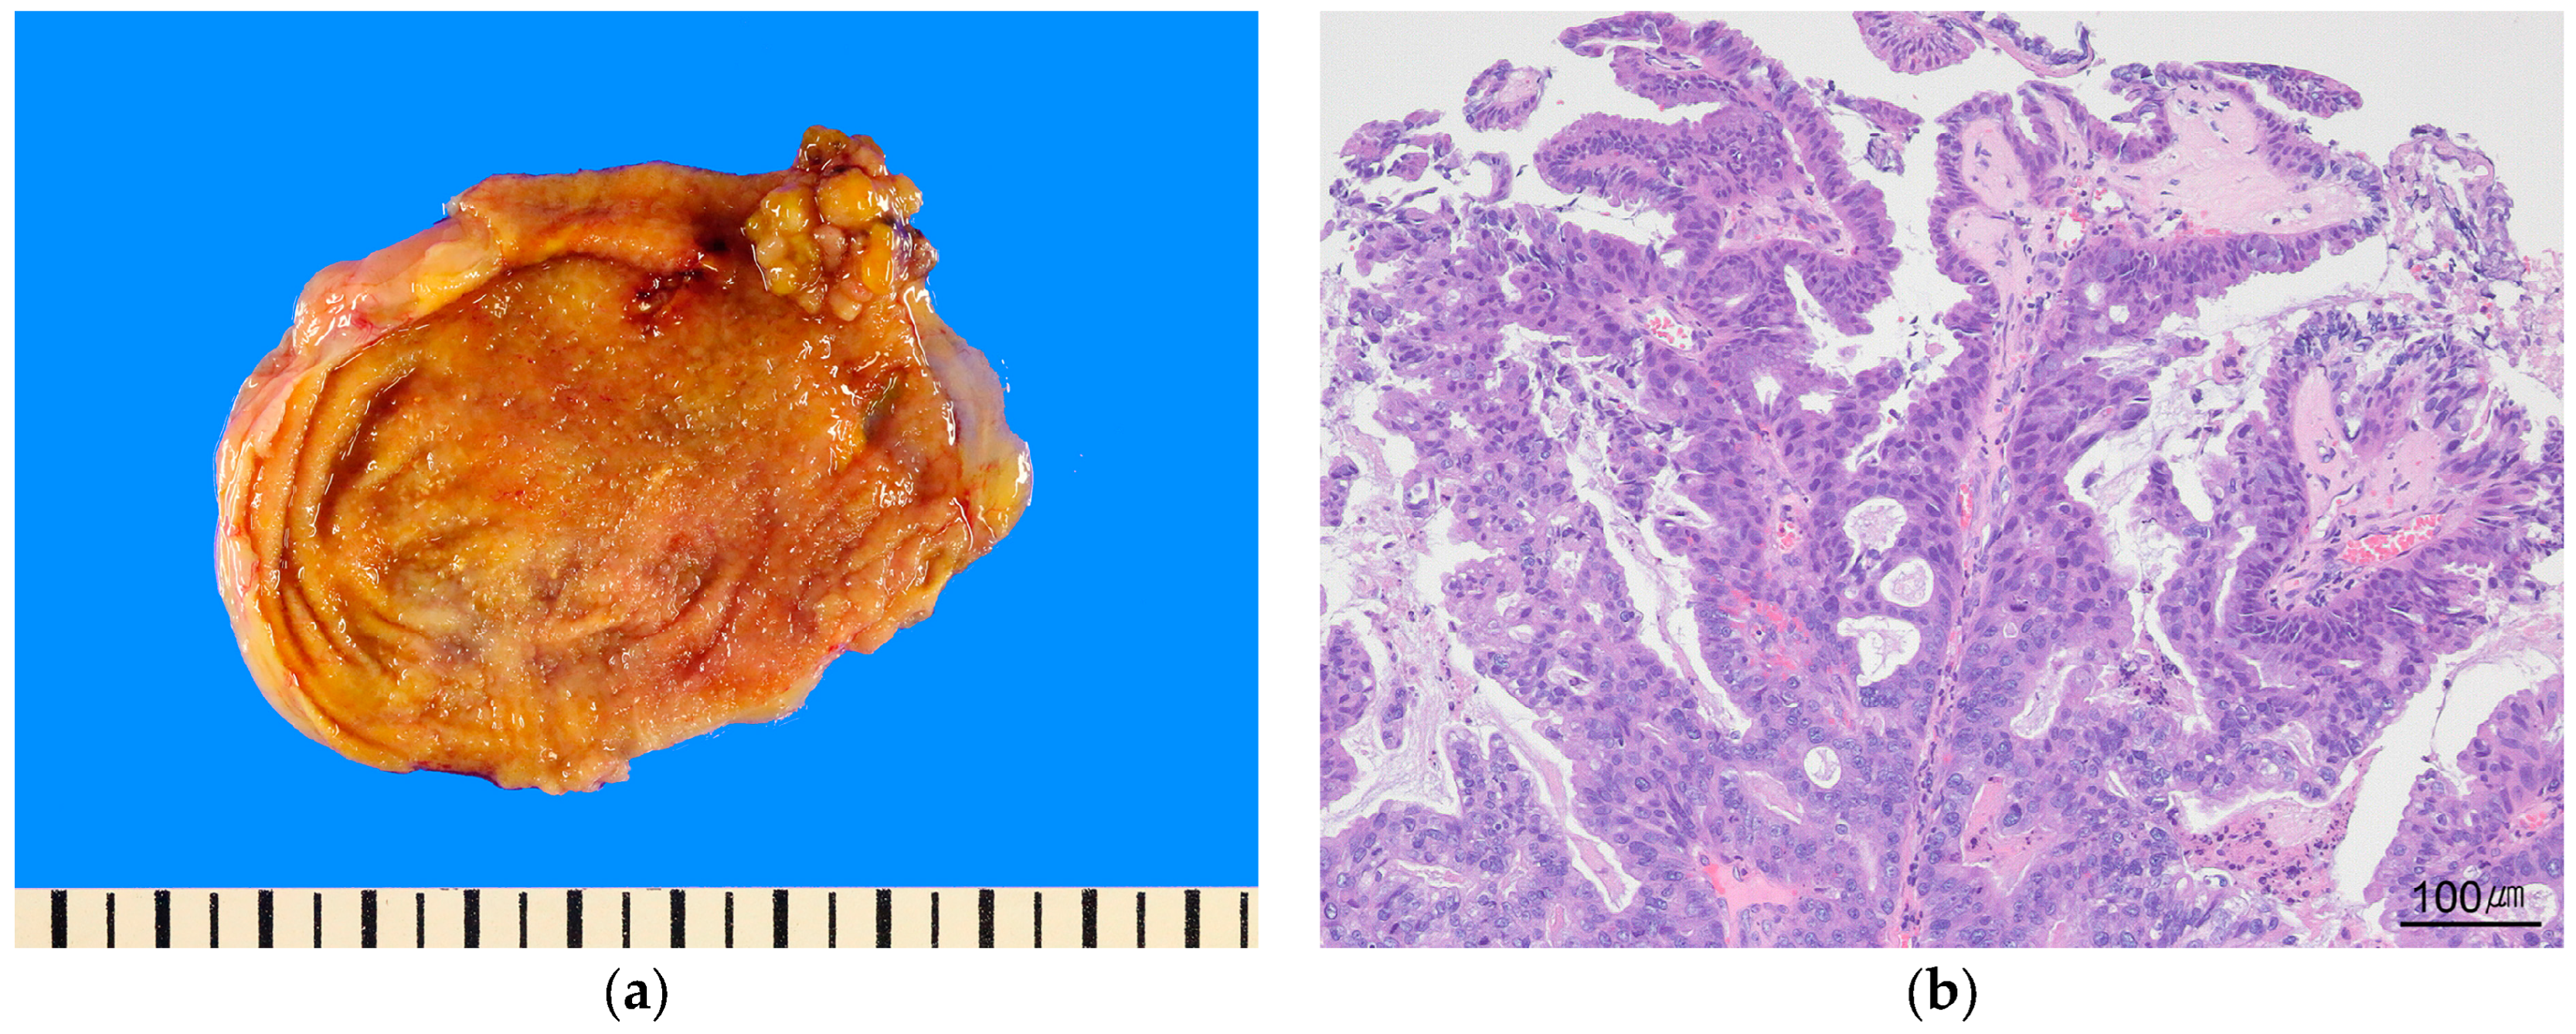
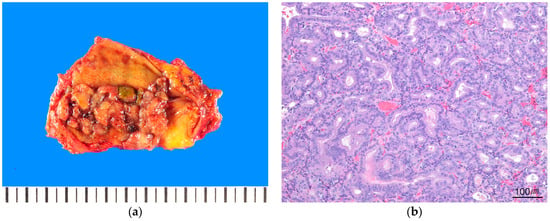
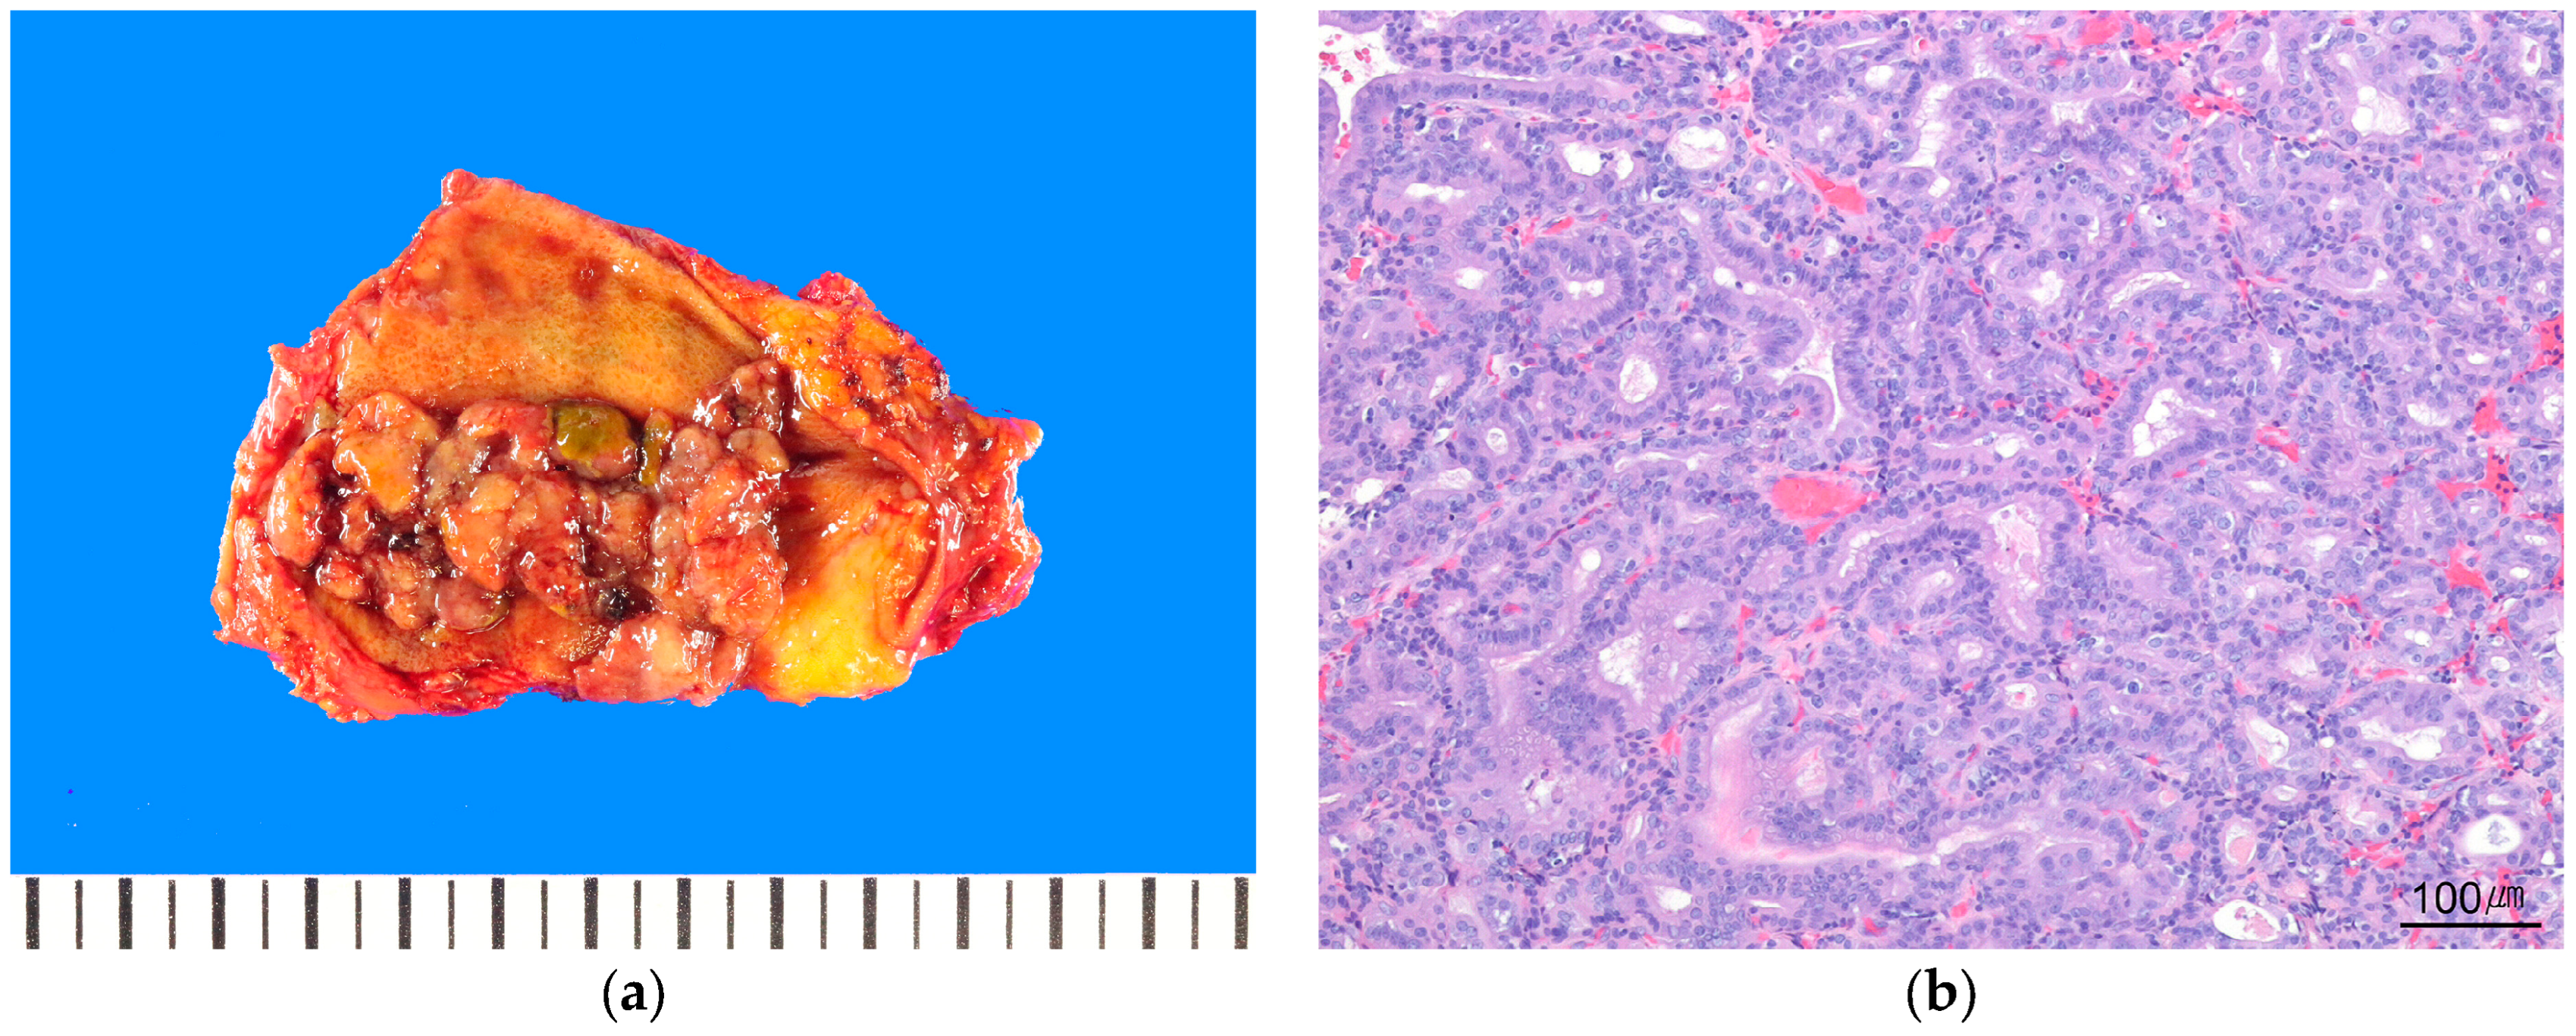
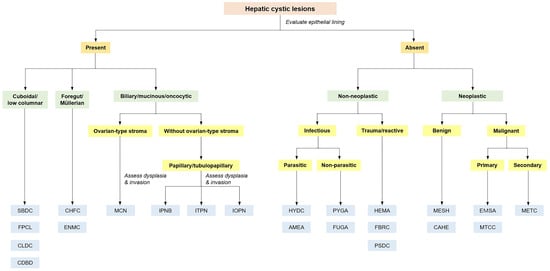
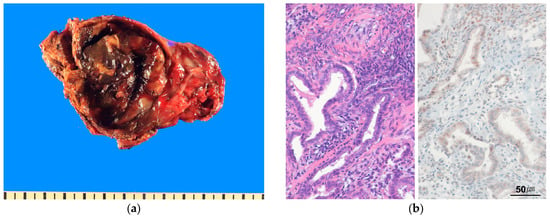
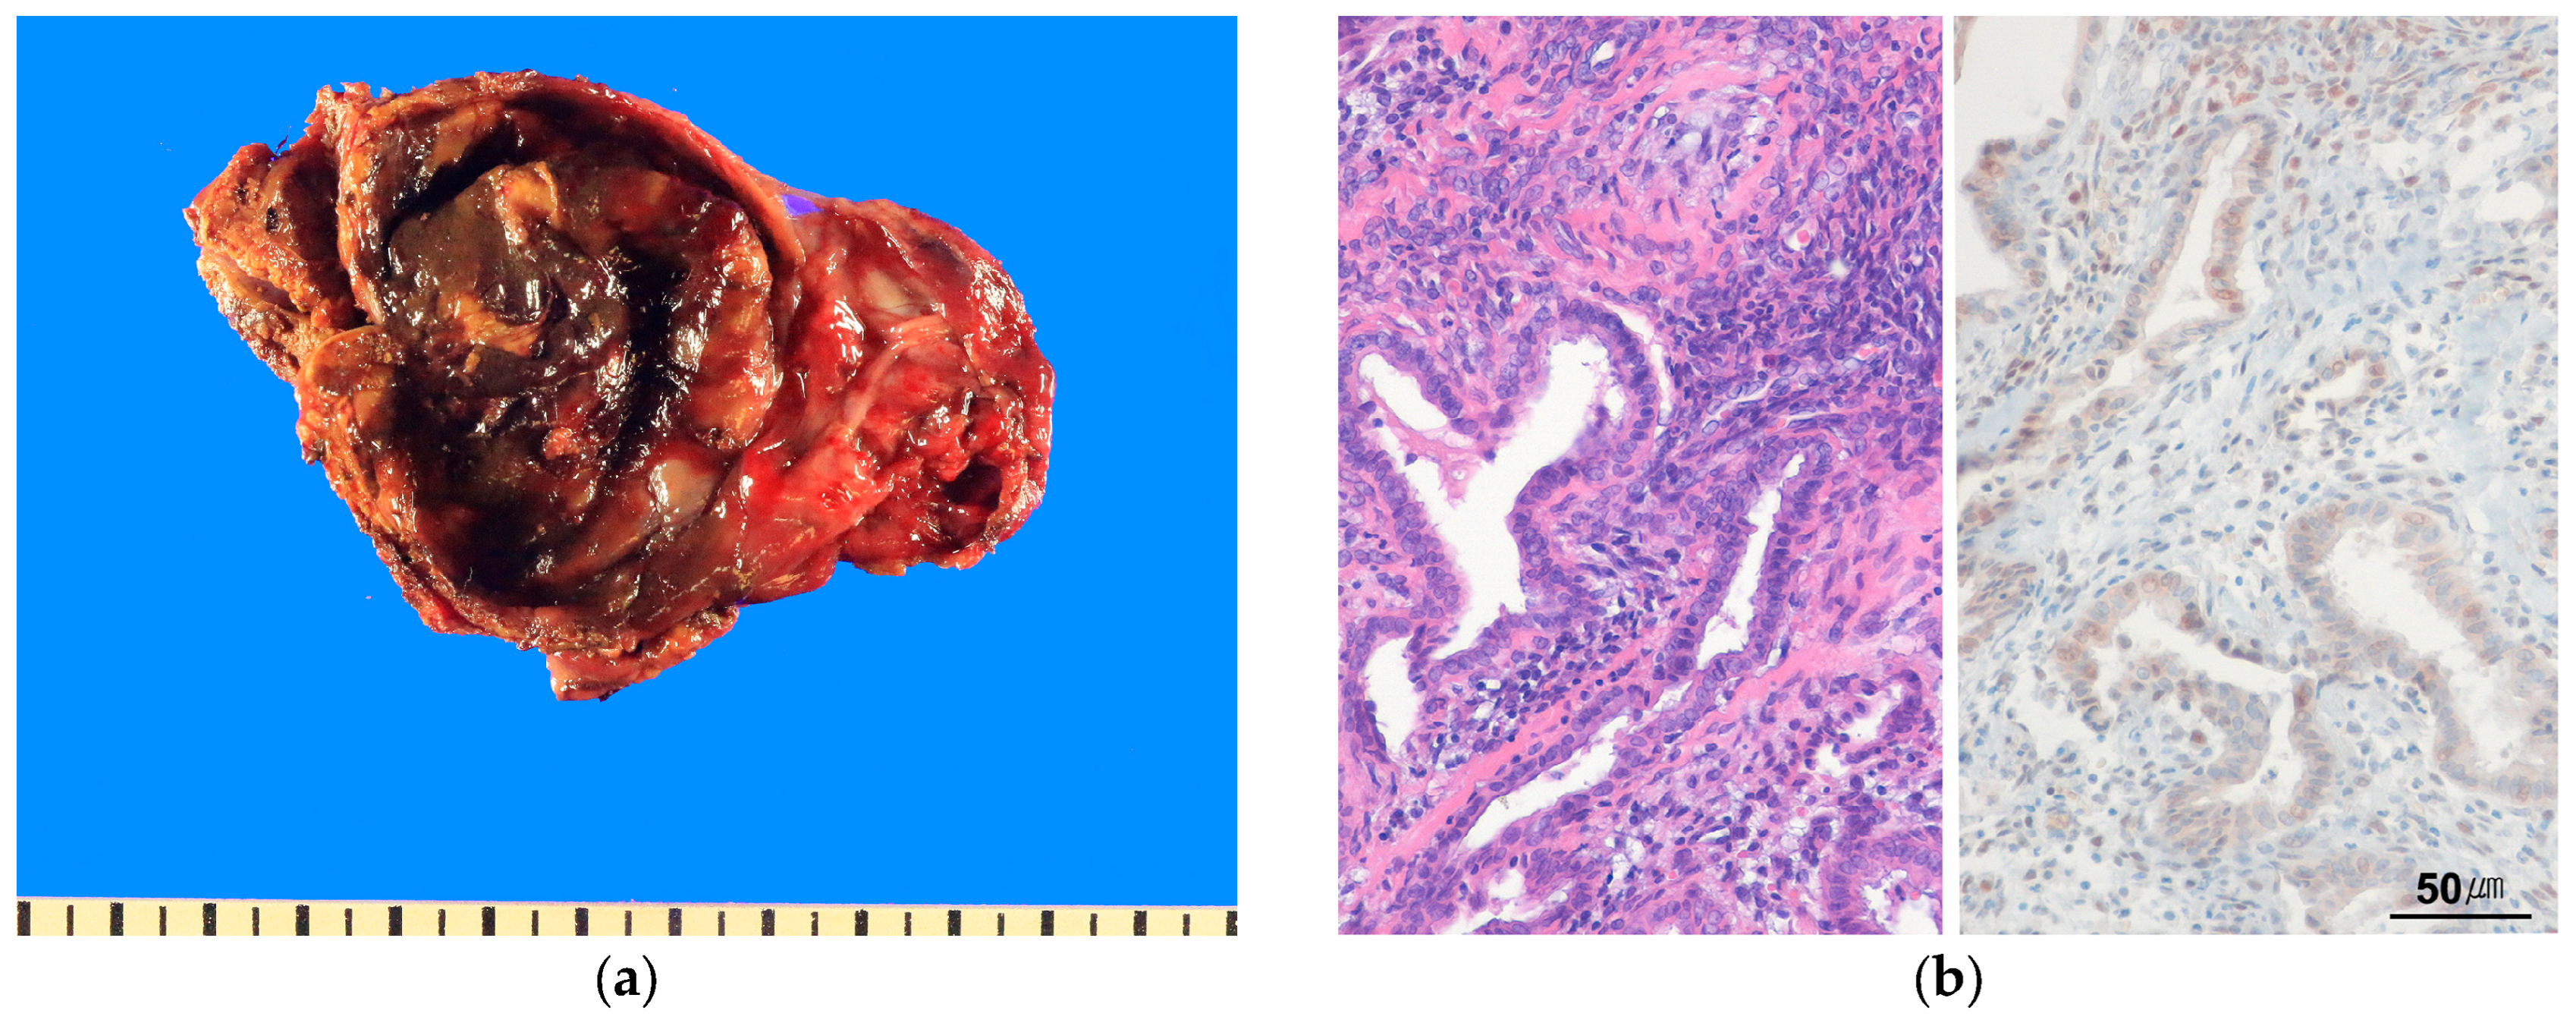
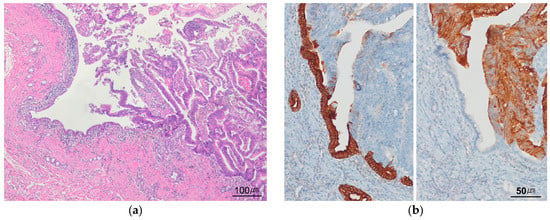
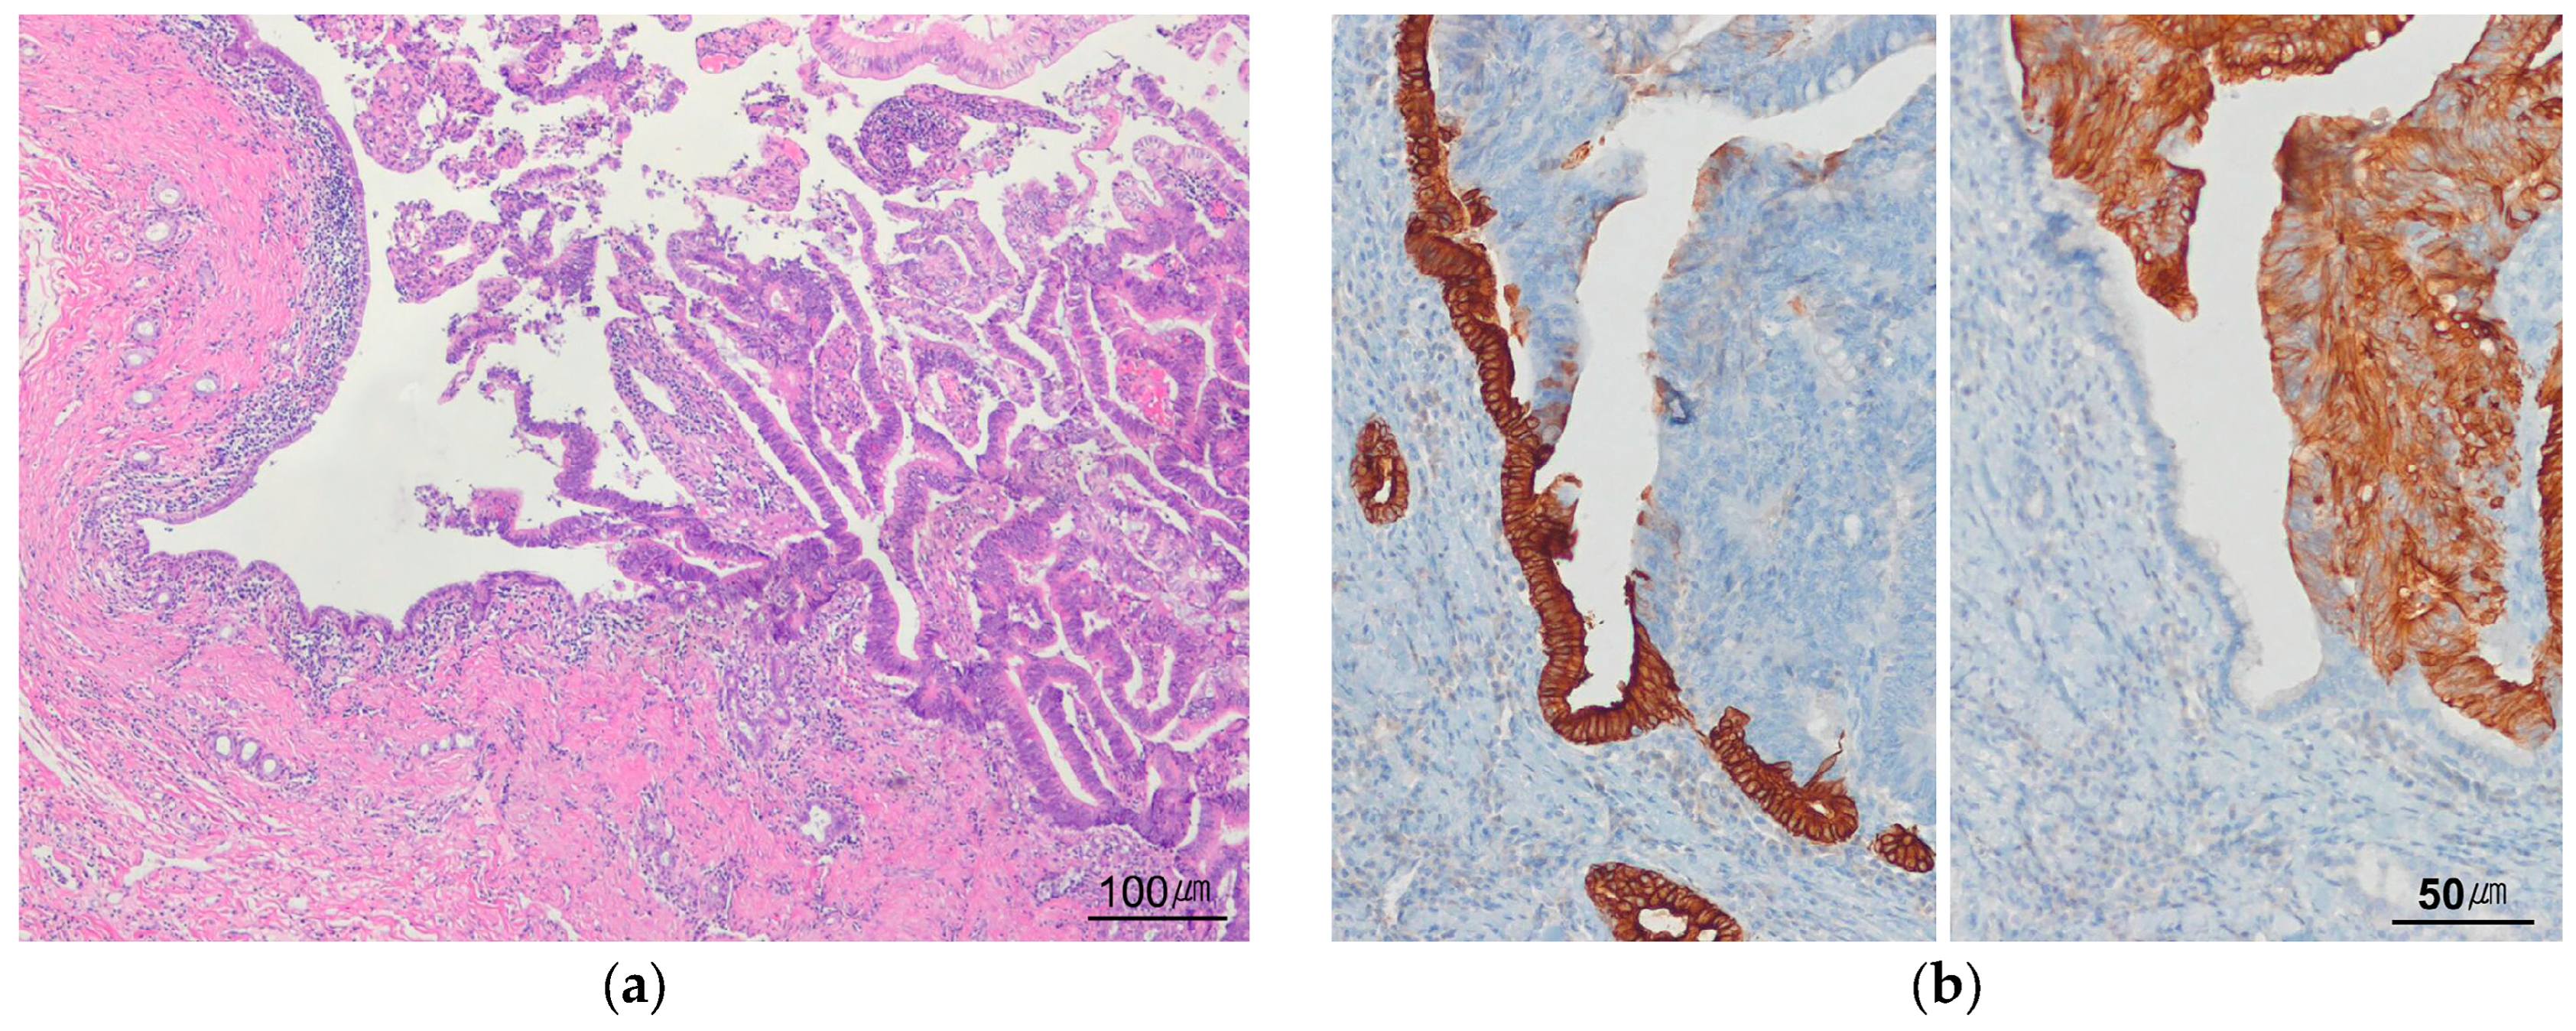

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.