


Abstract
Fibromyalgia is a complex chronic pain condition characterized by pervasive pain, persistent fatigue, and cognitive disturbances. Despite advances in understanding its neurobiological mechanisms, diagnosis largely relies on subjective symptom assessment and exclusion criteria, contributing to underdiagnosis and treatment delays. Recent research has increasingly focused on identifying objective biomarkers and leveraging digital phenotyping to improve diagnostic precision. Promising biomarkers include neuroimaging indicators of altered pain processing, neuroinflammatory signatures in cerebrospinal fluid and blood, and dysregulated neuroendocrine and autonomic patterns. In addition, metabolomics and transcriptomics have revealed molecular profiles associated with fibromyalgia pathophysiology. Concurrently, digital health tools (e.g., wearable sensors, ecological momentary assessment, and machine learning-based symptom clustering) offer opportunities for continuous, real-world data collection and individualized disease characterization. This body of work suggests that integrating biological and digital metrics could enable a transition from subjective to objective data-driven fibromyalgia classification, facilitating earlier diagnosis and improved therapeutic outcomes.
1. Introduction
Fibromyalgia is a chronic disorder characterized by extensive nociplastic pain (arising from altered nociceptive processing without tissue damage or somatosensory lesions) accompanied by systemic, neurocognitive, and mood disturbances, resulting in significant functional and socioeconomic burden [1]. Epidemiological data shows a global prevalence ranging from 0.2% to 6.6%, with a marked female predominance, suggesting potential contributions of sex-specific neuroimmune and hormonal mechanisms [2,3]. The clinical phenotype is characterized by chronic widespread pain, severe fatigue, sleep architecture disruption, and executive and attentional deficits commonly described as “fibro-fog” [4]. Additional symptoms typically include pronounced nociceptive hypersensitivity (allodynia and hyperalgesia), musculoskeletal stiffness, cephalalgia, functional gastrointestinal disorders including irritable bowel syndrome (IBS), and high rates of psychiatric comorbidities, including anxiety and depressive disorders [5]. Emerging evidence also highlights dysregulation of the autonomic nervous system and altered central pain processing pathways, which may be linked to increased symptom severity and variability [6,7]. Moreover, chronic inflammation and immune system perturbations have been proposed as underlying mechanisms that exacerbate both peripheral and central manifestations of the disorder (Figure 1) [8,9].
Figure 1.
Fibromyalgia manifests with several clinical features, including CNS symptoms, cephalic and temporomandibular symptoms, widespread myofascial pain and fatigue, abdominal and genitourinary complaints, cutaneous dysesthesia, and peripheral joint stiffness. These manifestations reflect the diffuse and heterogeneous somatic and neuropsychiatric symptom burden that characterizes this chronic pain syndrome.
This condition is progressively recognized as a central nociceptive processing disorder supported by maladaptive neuroimmune signaling within the central nervous system (CNS). Although its precise etiology remains elusive, converging evidence implicates maladaptive plasticity within pain-processing networks, characterized by impaired descending inhibitory pathways, enhanced excitatory neurotransmission, and sustained activation of glial cells [8]. These alterations may be precipitated or exacerbated by environmental stressors (e.g., physical trauma, infection, and chronic psychosocial stress) acting upon genetically or epigenetically susceptible individuals [9]. Neuroinflammation has emerged as a central pathophysiological component of fibromyalgia [10,11].
Beyond central mechanisms, accumulating evidence supports a significant contribution of peripheral neuroimmune alterations to fibromyalgia pathogenesis [12]. Peripheral nociceptors innervating skin and muscle tissues exhibit heightened excitability due to molecular sensitization of ion channels and receptors involved in pain transduction, such as transient receptor potential vanilloid (TRPV) channels, acid-sensing ion channels (ASICs), and purinergic P2X and P2Y receptors [13,14]. Some pro-inflammatory mediators released by immune cells within peripheral tissues further enhance nociceptor firing through cytokine-mediated signaling cascades, thus amplifying afferent nociceptive inputs [11,15].
The interplay between peripheral and central neuroimmune mechanisms forms a bidirectional feed-forward loop that drives both the initiation and maintenance of central sensitization [11]. Permanent peripheral nociceptive signaling can induce microglial priming and astrocyte reactivity in both the spinal cord and supraspinal structures, whereas CNS-derived inflammatory mediators can influence peripheral immune responses [15]. Central sensitization is associated with neurogenic inflammation, synaptic hyperexcitability, and maladaptive neuroplastic changes that underlie essential clinical features of fibromyalgia, including exaggerated tenderness, chronic pain amplification, peripheral edema, and cognitive dysfunction [16].
Given the multifactorial pathophysiology of fibromyalgia, it has become increasingly apparent that symptom-based clinical assessment alone is insufficient to delineate the heterogeneity of the disease phenotype. Accordingly, there has been an increasing focus on the development of supplementary diagnostic modalities designed to improve the clinical assessment [17]. These methodologies encompass neuroimmune biomarker analyses, advanced neuroimaging approaches, and neurophysiological evaluations, each providing a unique yet integrative insight into the fundamental pathophysiological processes [18]. At the molecular level, numerous studies have consistently reported elevated concentrations of several pro-inflammatory cytokines in cerebrospinal fluid (CSF) and skin tissues, such as IL-1β, IL-6, IL-8, IL-17, and TNF-α [19,20,21]. In addition to these pro-inflammatory mediators, chemokines including CCL2, CCL11, CXCL5, and CX3CL1 have been found to be increased, implicating enhanced leukocyte recruitment, glial activation, and neuroinflammatory signaling [22,23]. Anti-inflammatory cytokines, such as IL-10 and TGF-β, are often reported to be dysregulated, suggesting an impaired capacity for resolving neuroimmune activation [24,25]. Furthermore, peripheral mediators such as regulatory microRNAs (e.g., miR-4771 and miR-2115-3p) may contribute to peripheral neuroimmune interaction, thus reinforcing maladaptive pain processing [25]. Other factors, including substance P, are also increased in fibromyalgia patients, further potentiating peripheral and central sensitization through enhanced excitatory neurotransmission and glial activation [26].
On the other hand, advanced neuroimaging modalities have emerged as complementary tools for characterizing functional and structural aberrations within central pain-processing networks. Functional magnetic resonance imaging (fMRI) studies have repeatedly demonstrated hyperactivation of canonical nociceptive circuits (e.g., the insula, anterior cingulate cortex, and somatosensory cortices) upon nociceptive stimulation, concomitant with reduced engagement of descending inhibitory pathways, including those involving the periaqueductal gray and rostroventral medulla [27,28]. Diffusion tensor imaging (DTI) analyses have revealed microstructural abnormalities in white matter tracts implicated in pain modulation, such as the spinothalamic tract and corpus callosum, suggesting altered structural connectivity that may underpin abnormal pain processing [29]. Moreover, positron emission tomography (PET) using glial-specific tracers enables in vivo visualization of microglial and astrocytic activation, providing direct evidence of central neuroimmune dysregulation and glial contributions to chronic pain maintenance [30].
Finally, neurophysiological approaches serve as an additional layer of objective evaluation, permitting the quantification of nociceptive hyperexcitability and central sensitization. Quantitative sensory testing (QST) permits the systematic evaluation of thermal, mechanical, and vibratory detection and pain thresholds, thereby delineating the presence of allodynia, hyperalgesia, and other sensory disturbances that reflect the integrated contributions of peripheral and central mechanisms to symptom manifestation [31]. Pressure algometry provides additional objective indices of localized pain sensitivity, while evoked potential methodologies (e.g., laser-evoked and somatosensory evoked potentials) enable detailed temporal characterization of afferent nociceptive input and its cortical integration [32]. In parallel, microneurography offers high-resolution characterization of peripheral nerve fiber activity, associating aberrant afferent input with central hyperexcitability [33]. Collectively, these neurophysiological assessments link clinical symptomatology to quantifiable electrophysiological correlates, thereby strengthening the mechanistic understanding of fibromyalgia pathophysiology [27].
This review synthesizes current evidence on biological and digital biomarkers of fibromyalgia, highlighting their potential to enhance diagnostic accuracy. It discusses neuroimaging, neuroinflammatory, neuroendocrine, and autonomic markers, alongside molecular insights from metabolomics and transcriptomics, and examines digital phenotyping approaches. Through the convergence of these approaches, this review delivers a comprehensive synthesis of the field, delineates current knowledge gaps, and proposes future directions for objective diagnostics and personalized management of fibromyalgia.
2. Emerging Biological Biomarkers in Fibromyalgia
2.1. Neuroinflammatory and Immune Signatures
Growing evidence supports the concept that fibromyalgia is associated with measurable neuroinflammatory and immune-related alterations (Table 1), detectable both in CSF and peripheral blood [34,35]. Although fibromyalgia has long been classified as a non-inflammatory disorder, recent advances in immunological, proteomic, and transcriptomic research reveal a permanent low-grade neuroimmune activation profile [11]. These findings reinforce the hypothesis that immune signaling pathways contribute to central sensitization, pain amplification, fatigue, and cognitive dysfunction that characterize this disorder.
Table 1.
Central and peripheral biomarkers associated with neuroinflammation, immune dysregulation, and nociplastic pain mechanisms. Abbreviations: CSF (cerebrospinal fluid); IL-8 (interleukin-8); BDNF (brain-derived neurotrophic factor); NGF (nerve growth factor); IL-6 (interleukin-6); TNF-α (tumor necrosis factor alpha); IFN-γ (interferon gamma); CRP (C-reactive protein); S100A8 (S100 calcium-binding protein A8); S100A9 (S100 calcium-binding protein A9); VCAM1 (vascular cell adhesion molecule 1); CD163 (cluster of differentiation 163); SERPINA1 (serpin family A member 1); ANXA1 (annexin A1); AXIN1 (axis inhibition protein 1); STAMBP (STAM binding protein); SIRT2 (sirtuin 2); CCL2 (C-C motif chemokine ligand 2); CCL17 (C-C motif chemokine ligand 17); CXCL9 (C-X-C motif chemokine ligand 9); CXCL11 (C-X-C motif chemokine ligand 11); and BBB (blood–brain barrier).
CSF analyses have shown dysregulated neuroimmune signaling within the CNS of individuals with fibromyalgia [34]. Among the most consistently reported findings is the increase in IL-8, which plays a key role in glial activation, neuronal excitability, and nociceptive transmission [36]. Increased CSF IL-8 levels have been interpreted as an indicator of persistent microglial and astrocytic activation, potentially sustaining central sensitization processes [37]. Beyond IL-8, elevated CSF concentrations of excitatory neurotransmitters, particularly glutamate, have been reported in patients with fibromyalgia, consistent with heightened excitatory signaling and impaired inhibitory pain modulation [38]. Proteomic profiling of CSF has further identified differential expression of numerous inflammation-related and metabolic proteins, including apolipoprotein C-III, galectin-3-binding protein, malate dehydrogenase, and proSAAS-derived peptides, implicating lipid metabolism, immune signaling, mitochondrial dysfunction, and neuropeptide processing in fibromyalgia pathophysiology [34,39]. Other emerging evidence shows the involvement of biomarkers indicative of subtle neuronal injury, including neurofilament light chain, may be altered in fibromyalgia patients, although this remains an area of investigation [40].
Peripheral blood studies have revealed a broad spectrum of immune abnormalities, reflecting systemic low-grade inflammation rather than classical autoimmune pathology [45]. Numerous studies have reported elevated circulating levels of pro-inflammatory cytokines, such as IL-6, IL-8, TNF-α, and IFN-γ [46]. These pro-inflammatory cytokines are recognized for modulating nociceptor sensitivity, synaptic plasticity, and neuroendocrine regulation, and their upregulation may underlie the widespread pain, fatigue, and sleep disturbances observed in fibromyalgia [47]. Acute-phase reactants, such as C-reactive protein (CRP) are also increased in several fibromyalgia patients, reinforcing the concept of chronic, low-intensity inflammation [48].
Beyond circulating cytokines, peripheral blood transcriptomic analyses have identified different immune gene expression signatures in fibromyalgia patients. Upregulation of interferon-regulated genes and inflammation-associated transcripts, including S100A8, S100A9, VCAM1, CD163, SERPINA1, and ANXA1, has been observed in B-cell populations [49]. These findings indicate chronic immune activation and dysregulated leukocyte function, which may impact neuroimmune communication via cytokine signaling and interactions with the blood–brain barrier (BBB) [50]. Proteomic platforms have additionally expanded the list of candidate serum biomarkers, identifying elevations in immune-modulatory proteins such as AXIN1, STAMBP, SIRT2, and additional chemokines and signaling molecules (CCL2, CCL17, CXCL9, and CXCL11), which are associated with symptom severity and disease burden [22,51].
Neurotrophic and neuroimmune signaling pathways appear to be altered in fibromyalgia. Brain-derived neurotrophic factor (BDNF), which plays a key role in synaptic plasticity and pain sensitization, is frequently elevated in serum and has been associated with intensified pain sensitivity and cognitive symptoms [41]. Alterations in substance P, nerve growth factor (NGF), along with other neuropeptides that communicate with the immune system, support a model in which peripheral immune activation and neuroinflammation converge to sustain nociplastic pain [42,43]. Importantly, correlations between peripheral inflammatory markers and CSF cytokine concentrations are generally weak, underscoring the huge complexity of immune signaling across the BBB and suggesting that peripheral biomarkers may partly reflect central neuroinflammatory processes [44].
2.2. Neuroendocrine and Autonomic Biomarkers
One of the most consistently reported findings in fibromyalgia is HPA axis dysregulation, primarily evidenced by abnormalities in cortisol secretion [52]. Numerous studies have documented flattened diurnal cortisol rhythms, with reduced morning cortisol levels, blunted cortisol awakening response (CAR), and reduced circadian amplitude [53,54,55,56]. These alterations suggest impaired adrenal responsiveness and disrupted central regulation at the level of the hypothalamus or pituitary [57]. Basal hypocortisolism, particularly under stress-free conditions, is usually observed and is thought to reflect chronic overexposure to stressors leading to an exhausted HPA axis phenotype [58]. Salivary, plasma, and urinary cortisol measurements often reveal lower total cortisol output across the day, alongside increased intraindividual variability [59,60,61].
At the molecular level, altered regulation of corticotropin-releasing hormone (CRH) has been shown in fibromyalgia patients [62]. Several patients show elevated basal CRH concentrations in CSF, despite normal or reduced peripheral cortisol levels, indicating impaired downstream signaling or adrenal insensitivity [63]. This dissociation suggests altered pituitary responsiveness to CRH, potentially mediated by changes in receptor sensitivity or post-receptor signaling pathways [64].
Dysregulation of glucocorticoid receptor (GR) signaling represents an additional key molecular biomarker domain. Reduced GR sensitivity has been proposed based on altered expression of GR-related genes and disrupted negative feedback control of the HPA axis [65]. Polymorphisms and epigenetic modifications in several genes, such as NR3C1, which encodes the GR, have been linked to fibromyalgia symptom severity and stress reactivity [66]. Aberrant DNA methylation patterns in GR-regulatory regions may contribute to persistent dysregulation of cortisol signaling, linking early-life stress and trauma to long-term neuroendocrine vulnerability in fibromyalgia patients [67].
In parallel to HPA axis alterations, fibromyalgia is associated with pronounced autonomic imbalance, typically characterized by sympathetic predominance and reduced parasympathetic activity [68]. Heart rate variability (HRV) studies consistently show reduced overall HRV, decreased high-frequency components, and elevated low-frequency to high-frequency ratios, reflecting reduced vagal tone and impaired autonomic adaptability [69]. This autonomic profile persists during stress exposure, indicating a chronic state of autonomic rigidity rather than situational dysregulation [70]. Catecholaminergic signaling is altered in fibromyalgia, with abnormalities in norepinephrine and epinephrine dynamics observed at both central and peripheral levels [71]. Reduced CSF norepinephrine levels, coupled with excessive sympathetic activation in response to many stressors, suggest impaired sympathetic regulation [72]. Altered sensitivity of adrenergic receptors, potentially β2-adrenergic receptors, mediate pain perception [73]. Genetic polymorphisms affecting genes encoding catechol-O-methyltransferase (COMT) are among the most robustly replicated genetic associations in fibromyalgia, associating impaired catecholamine metabolism with heightened pain sensitivity and stress vulnerability [74].
Autonomic dysregulation in fibromyalgia is further reflected in abnormalities of baroreflex sensitivity and cardiovascular control [75]. Dysregulated baroreceptor responsiveness contributes to orthostatic intolerance, dizziness, and exercise intolerance commonly reported by fibromyalgia patients [76]. Finally, dysregulation of melatonin has emerged as a crucial neuroendocrine biomarker in fibromyalgia patients [77]. Abnormal nocturnal melatonin secretion patterns have been shown in conjunction with non-restorative sleep, circadian rhythm disturbances, and increased pain sensitivity [78].
2.3. Omics-Based Biomarker Discovery
Omics technologies, particularly metabolomics and transcriptomics, have emerged as critical tools to unravel the molecular networks underpinning fibromyalgia, revealing a constellation of potential biomarkers and mechanistic insights (Table 2) [79,80]. Metabolomic profiling has shown alterations in some amino acid homeostasis, mostly branched-chain amino acids (BCAAs), leucine, isoleucine, and valine, which are frequently elevated, implicating disrupted skeletal muscle energy metabolism, impaired mitochondrial oxidative phosphorylation, and activation of mTOR signaling pathways [81]. Aromatic amino acids, such as phenylalanine, tyrosine, and tryptophan, display differential plasma and CSF levels, reflecting an imbalance in catecholaminergic and serotonergic neurotransmission [82,83]. Tryptophan metabolism is significantly dysregulated, with increased kynurenine, 3-hydroxykynurenine, quinolinic acid, and xanthurenic acid, alongside reduced serotonin and melatonin precursors, indicating enhanced neuroinflammatory signaling, excitotoxicity via NMDA receptor activation, and disruption of circadian regulation [84,85]. Glutamine and glutamate ratios are also disrupted, consistent with altered glutamatergic neurotransmission and central sensitization, while glycine and GABA levels suggest reduced inhibitory neurotransmission in central nociceptive circuits [86]. Arginine, citrulline, and ornithine imbalances point to dysregulated nitric oxide synthase (NOS) activity, endothelial dysfunction, and attenuated vasodilatory responses, which might contribute to tissue hypoperfusion and pain sensitization [87].
Table 2.
Key findings and implicated mechanisms identified by omics approaches in metabolites, transcriptomics, and pathways related to metabolism, inflammation, and neurotransmission. Abbreviations: BCAAs (branched-chain amino acids), GABA (gamma-aminobutyric acid), TCA (tricarboxylic acid), TLR (Toll-like receptor), and ATP (adenosine triphosphate).
Lipidomic alterations are among the most consistently reported metabolic signatures in fibromyalgia. Elevated ceramides (C16:0, C18:0, C20:0), sphingomyelins (SM d18:1/16:0, SM d18:1/18:0), lysophosphatidylcholines (LPC 16:0, LPC 18:0), and phosphatidylcholines (PC 34:1, PC 36:2) suggest dysregulated sphingolipid and glycerophospholipid metabolism, which might modulate apoptosis, neuroinflammation, and membrane fluidity [88]. On the other hand, fibromyalgia patients showed significantly increased oxidative stress markers (TOS, TAS, MDA, and OSI) compared with controls, indicative of reduced oxidative lipid damage and deficient anti-inflammatory regulation [89]. Increased circulating acylcarnitines (C2-C18) denote incomplete fatty acid β-oxidation and mitochondrial dysfunction [90,91]. Moreover, disturbances in eicosanoid metabolism, like increased prostaglandin E2 (PGE2), thromboxane B2, and leukotriene B4, highlight activation of cyclooxygenase (COX) and lipoxygenase (LOX) pathways contributing to systemic and neuroinflammation [92]. Purine metabolism is also dysregulated, with increased plasma and cerebrospinal hypoxanthine, xanthine, uric acid, and inosine, suggesting augmented reactive oxygen species (ROS) production, oxidative stress, and nucleotide turnover [93,94]. TCA cycle intermediates, including citrate, α-ketoglutarate, succinate, fumarate, and malate, are dysregulated, pointing to mitochondrial dysfunction, compromised electron transport chain activity, and a metabolic reprogramming toward anaerobic glycolysis, as evidenced by increased lactate and pyruvate levels [95]. Increased creatine, creatinine, and guanidinoacetate levels suggest perturbed phosphagen metabolism, contributing to skeletal muscle fatigue and energy insufficiency [96].
Transcriptomic analyses reinforce these metabolic findings by identifying dysregulated genes in pathways governing immune activation, neurotransmission, mitochondrial function, oxidative stress response, and cellular metabolism. Peripheral blood mononuclear cell (PBMC) transcriptomes consistently reveal upregulation of proinflammatory cytokines and chemokines, including IL-6, IL-1β, TNF-α, IL-17, CCL2, CCL5, CXCL8, and CXCL10, accompanied by downregulation of anti-inflammatory mediators such as IL-10, TGF-β1, and SOCS3 [97]. Toll-like receptor (TLR) signaling genes, especially TLR2, TLR4, and MyD88, are also upregulated, suggesting an innate immune response [98,99]. Genes encoding mitochondrial respiratory chain components, such as ND4, CyB, NRF-1, Tfam, and UCP2, are consistent with impaired electron transport chain activity and reduced ATP production [100,101]. Glycolytic and fatty acid oxidation genes, including LDH, CPT1, and acyl-CoA dehydrogenases, are differentially expressed, supporting metabolomic evidence of altered energy metabolism [102]. Finally, several oxidative stress-response genes, such as SOD, GPX, NQO1, HO-1/HMOX1, are dysregulated in fibromyalgia patients, indicating upregulation and activation of oxidative stress-response pathways [103].
Conversely, altered expression of neurotransmission-related genes has been reported in fibromyalgia patients. Decreased expression of inhibitory neurotransmission genes, including GABRB3, is consistent with a central excitatory-inhibitory imbalance potentially underlying hyperalgesia and allodynia [104]. Finally, dysregulation of circadian rhythm- and stress-response-associated genes, like NR3C1, suggests a link between chronic stress, sleep disturbances, impaired proteostasis, and fibromyalgia pathophysiology [105].
The integration of metabolomic and transcriptomic signatures enables patient stratification and mechanistic insight while forming the basis for precision medicine [106]. This approach facilitates the identification of fibromyalgia endophenotypes and the development of targeted interventions [107]. Future studies integrating multi-omics data with longitudinal clinical phenotyping, neuroimaging, microbiome profiling, and machine-learning approaches will be crucial to refine molecular networks, validate robust biomarkers, and translate molecular findings into diagnostic, prognostic, and therapeutic tools for fibromyalgia [106,108,109,110].
3. Digital Phenotyping Approaches in Fibromyalgia
3.1. Neuroimaging Markers of Altered Pain Processing
Fibromyalgia is increasingly recognized as a disorder of central pain processing rather than merely peripheral nociception, and neuroimaging studies have been pivotal in elucidating the neural substrates underlying its clinical manifestations [111]. Functional magnetic resonance imaging (fMRI) studies consistently demonstrate abnormal activation patterns in response to both experimentally induced and spontaneous pain [112]. Hyperactivation of the insular cortex, particularly the anterior insula, reflects heightened interoceptive and affective processing of nociceptive signals, whereas increased activity in the anterior cingulate cortex (ACC) is associated with enhanced emotional appraisal and salience attribution to painful stimuli [113,114,115,116]. Simultaneously, hypoactivation or reduced modulation within the prefrontal cortex (PFC) and periaqueductal gray (PAG) suggests impaired engagement of top-down inhibitory circuits, which normally attenuate pain perception [117,118].
Resting-state fMRI analyses provide complementary insights by revealing intrinsic network abnormalities independent of stimulus presentation [119]. Increased functional connectivity between the default mode network (DMN) and key pain-processing regions, including the insula and ACC, has been linked to persistent rumination on pain and maladaptive attentional biases [120]. Simultaneously, reduced connectivity between the DMN and executive control networks, especially within dorsolateral prefrontal and parietal cortices, correlates with cognitive impairments frequently reported in fibromyalgia patients, including deficits in working memory, cognitive flexibility, and attentional control [121]. Altered salience network connectivity, encompassing the ACC and anterior insula, further reflects abnormal detection and prioritization of sensory inputs, suggesting that fibromyalgia patients exhibit increased sensitivity not only to nociceptive stimuli but also to environmental stressors that may exacerbate pain perception [122].
Structural neuroimaging has revealed convergent evidence of gray and white matter abnormalities. Voxel-based morphometry (VBM) studies report reductions in gray matter volume in regions integral to pain and affective processing, such as the ACC, insula, thalamus, and prefrontal cortices [123,124]. These changes are interpreted as neuroplastic adaptations to chronic nociceptive input, potentially reflecting maladaptive sensitization or excitotoxicity [125]. Diffusion tensor imaging (DTI) further identifies microstructural alterations in white matter pathways connecting the PFC, limbic system, and somatosensory regions, implicating disruptions in circuits mediating top-down modulation of pain and affective responses [126].
Progress in multimodal neuroimaging has enhanced our understanding of underlying mechanisms. Magnetic resonance spectroscopy (MRS) studies indicate region-specific neurotransmitter imbalances, such as elevated glutamate levels in the insula and decreased GABA contents in prefrontal regions [127]. Positron emission tomography (PET) imaging has also demonstrated altered μ-opioid receptor availability in the ACC, PFC, and amygdala, further supporting the notion of impaired endogenous analgesic mechanisms [128].
3.2. Wearable Technologies and Continuous Physiological Monitoring
The advent of wearable technologies has revolutionized the study and management of fibromyalgia. Contemporary wearable devices, including wrist-worn actigraphy units, chest straps, smart textiles, and adhesive biosensors, allow for the continuous, high-resolution collection of physiological data encompassing physical activity, sleep architecture, and autonomic nervous system function [129]. Integrated accelerometry and gyroscopic sensors allow detailed measurement of daily movement patterns, capturing step counts, activity levels, postural changes, and periods of inactivity [130]. In fibromyalgia, where patients often modulate activity to avoid pain exacerbation, these continuous metrics permit objective assessment of low-level activity fluctuations and fatigue accumulation that persist unseen by retrospective self-reports or clinical observation [131,132]. Beyond simple activity measures, these devices enable the correlation of physical behavior with pain flares, offering insight into the bidirectional interactions between activity limitation, energy expenditure, and symptom severity [133].
Sleep disturbances, a pivotal component of fibromyalgia pathology, can be evaluated with unparalleled granularity through wearable technologies combining actigraphy with photoplethysmography, skin temperature, and electrodermal activity sensors [134,135]. Continuous monitoring captures sleep onset latency, nocturnal awakenings, sleep fragmentation, and sleep-stage distribution, including non-rapid eye movement (NREM) and rapid eye movement (REM) phases [136]. This is relevant in fibromyalgia, where disruptions in slow-wave sleep are implicated in central sensitization and impaired descending pain inhibition [137]. Integration of sleep and activity data allows researchers to model circadian patterns and examine the temporal relationships among daytime fatigue, nocturnal arousals, and autonomic fluctuations. Such analyses provide mechanistic insight into the interplay between restorative sleep deficits and symptom exacerbation, potentially informing targeted interventions [138,139].
Autonomic nervous system monitoring through wearable sensors, including continuous HRV, skin conductance, peripheral temperature, and respiratory rate, reveals physiological dysregulation frequently observed in fibromyalgia [140]. Altered sympathetic-parasympathetic balance, manifesting as reduced HRV, heightened sympathetic tone, and blunted parasympathetic responses, correlates with heightened pain perception, reduced stress resilience, and impaired sleep quality [68]. Prolonged, multimodal monitoring permits temporal mapping of autonomic fluctuations relative to activity and sleep patterns, revealing periods of vulnerability that might precede pain flare-ups or cognitive fatigue [141]. Furthermore, the application of advanced signal processing and machine learning to these datasets allows predictive modeling of symptom trajectories, providing a framework for personalized and proactive management strategies [142].
Despite the potential of wearable technologies, some limitations merit careful consideration. Sensor accuracy can be influenced by device placement, motion artifacts, and inter-individual variability in skin characteristics, cardiovascular responsiveness, or body composition, potentially confounding heart rate, electrodermal, and temperature measurements [143,144]. Patient adherence is an essential concern, as chronic pain, fatigue, tactile hypersensitivity, or discomfort from prolonged device wear may reduce compliance, introducing biases in data acquisition [145]. The interpretation of continuous, multimodal data in fibromyalgia is further complicated by the heterogeneous nature of the disorder, necessitating longitudinal baselines and analytical frameworks to distinguish pathological alterations from normal physiological variability [106,142]. Moreover, clinical integration of wearable-derived data prompts practical and ethical considerations, such as data privacy, storage, interoperability with electronic health records, and the need for actionable insights to facilitate therapeutic strategy [146]. Addressing these challenges is essential to ensure that wearable technologies provide not only precise and ecologically reliable measurements and actionable insights for patient-specific management planning, mechanistic understanding, and ultimately the enhancement of quality of life for fibromyalgia patients.
3.3. Ecological Momentary Assessment and Real-World Symptom Capture
Ecological Momentary Assessment (EMA) is a methodological approach particularly well suited to the study of fibromyalgia [147]. This method involves the real-time collection of data in participants’ natural environments, typically through brief questionnaires, mobile applications, or electronic devices. EMA captures experiences, symptoms, and behaviors as they occur in daily life, thereby reducing the recall bias inherent in retrospective self-reports [148]. Traditional retrospective assessments, often administered during clinical visits, are impaired by recall bias, temporal averaging, and an underrepresentation of real-world contexts [149]. Traditional retrospective assessments, often conducted through questionnaires during clinic visits, are limited by recall bias, temporal averaging, and abstraction from real-world contexts [150].
EMA has been particularly informative in elucidating the complex temporal dynamics of fibromyalgia symptoms. Pain, fatigue, cognitive dysfunction (“fibro fog”), sleep disturbances, and affective symptoms fluctuate not only across days but also within the same day. High-frequency EMA sampling has demonstrated meaningful diurnal patterns, such as morning stiffness, transient mid-day symptom relief, and evening symptom worsening, which are often masked by daily or weekly summary measures [150]. Capturing these rhythms provides insight into potential links with circadian regulation, sleep quality, autonomic functioning, and daily activity cycles, and helps explain why patients with similar average symptom levels might experience very different degrees of functional impairment [138].
Beyond diurnal variation, EMA enables the examination of short-term symptom instability, an increasingly recognized feature of fibromyalgia [151]. Moment-to-moment symptom variability and abrupt exacerbations have been associated with central sensitization, emotional dysregulation, and maladaptive coping strategies. Importantly, EMA-derived indices of symptom volatility might capture disease burden more accurately than mean symptom intensity and appear to be closely associated with disability, perceived lack of control, and reduced quality of life [152].
EMA is also uniquely suited to examining the contextual sensitivity of fibromyalgia symptoms. Fibromyalgia symptoms are dynamically modulated by many environmental, behavioral, and psychosocial factors, like physical activity, stress exposure, social interactions, affective states, and sleep quality. By measuring symptoms in close temporal alignment with contextual variables, EMA supports the identification of real-world symptom triggers and protective factors [153].
The relationship between physical activity and fibromyalgia symptoms illustrates the added value of EMA. Although exercise is widely recommended, patients usually report activity-related symptom exacerbation [154]. EMA studies, integrated with wearable sensors, demonstrate that activity-symptom relationships are highly context-dependent and influenced by factors like baseline fatigue, emotional state, prior sleep, and pacing strategies [155]. These individualized activity-symptom contingencies are difficult to detect using traditional methods but are essential for developing personalized rehabilitation and self-management interventions [156].
Cognitive and affective symptoms, including concentration difficulties, anxiety, and depressive affect, also show substantial variability [157]. EMA research suggests that these symptoms often co-vary with pain and fatigue but may also fluctuate independently, especially in response to stress or cognitive load. EMA designs enable the modeling of short-term, bidirectional relationships between symptoms and affect, contributing to a more refined understanding of symptom maintenance mechanisms [158].
3.4. Machine Learning and Data-Driven Patient Stratification
Machine learning (ML) enables systematic analysis of the complex heterogeneity inherent in fibromyalgia [94]. Conventional analytical approaches usually fail to capture the nonlinear interactions among symptoms, whereas ML combines high-dimensional clinical, psychosocial, behavioral, and biological data to delineate patient subgroups and characterize symptom trajectories [159].
Unsupervised learning, mainly symptom clustering through methods like k-means, hierarchical clustering, and Gaussian mixture models, consistently demonstrates that fibromyalgia encompasses heterogeneous phenotypes differing in pain intensity, fatigue, sleep disturbances, mood, and functional impairment, often independent of demographic variables [160]. Predictive modeling approaches, such as random forests, gradient boosting, and neural networks, permit prediction of outcomes including symptom severity, loss of function, quality of life, and treatment response [161]. Incorporating longitudinal data via recurrent neural networks or temporal convolutional models captures intra-individual symptom fluctuations, providing early warning signals and informing personalized interventions [162]. Integrating unsupervised clustering with supervised predictive modeling enhances clinical relevance by refining phenotypic stratification and prognostic prediction [163].
4. Clinical Implications and Translational Potential
Patient stratification constitutes a pivotal component in optimizing therapeutic outcomes in fibromyalgia [164]. This disorder manifests pronounced phenotypic heterogeneity, which can differentially influence disease progression and therapeutic response [165]. Consequently, conventional one-size-fits-all therapeutic approaches are intrinsically limited, underscoring the need for precision medicine frameworks that integrate systematic, multidimensional patient stratification [166].
Pharmacologic interventions in fibromyalgia exhibit substantial interindividual variability, consistent with underlying mechanistic heterogeneity. Serotonin-norepinephrine reuptake inhibitors (SNRIs), including duloxetine and milnacipran, modulate descending inhibitory pain pathways and often show enhanced efficacy in patients exhibiting prominent affective dysregulation and central sensitization [167]. Gabapentinoids, like pregabalin and gabapentin, regulate VGCCs to attenuate excitatory neurotransmission, showing benefit in individuals with hyperalgesia or allodynia [168]. Tricyclic antidepressants provide analgesic and sleep-modulatory effects, though their anticholinergic profile can limit tolerability, particularly in older adults [169]. Novel pharmacologic approaches, including low-dose naltrexone, act by attenuating microglial activation and neuroinflammatory cascades, offering potential therapeutic avenues for patients with heightened central immune signaling [170]. These observations illustrate the importance of mechanistically informed treatment selection to improve clinical outcomes and reduce the reliance on empiric trial-and-error approaches.
Non-pharmacologic interventions also demonstrate variable effectiveness according to individual neuropsychological and psychosocial profiles. Cognitive-behavioral therapy (CBT) targets maladaptive mental appraisals and coping strategies [171], while mindfulness-based stress reduction (MBSR) interventions potentiate parasympathetic tone, emotional resilience, and attentional control [172]. Graded exercise programs (GEP) involve dose titration tailored to baseline fatigue, pain sensitivity, and cardiovascular function to maximize benefit while minimizing symptom exacerbation [173,174]. Neurofeedback and other neuromodulation techniques aim to normalize aberrant cortical network activity associated with central pain processing and emotional regulation [175]. Integration of these behavioral and neuromodulatory strategies with pharmacologic interventions allows a multidimensional, personalized approach, where treatment is matched to both phenotypic and mechanistic characteristics, ultimately improving functional outcomes [166].
Translational research in fibromyalgia increasingly focuses on targeting mechanistic pathways implicated in symptom generation and maintenance. Central sensitization, reflected in hyperexcitability of nociceptive neurons and impaired inhibitory control within the CNS, remains a primary focus for therapeutic modulation [176]. Neuroinflammatory processes, mediated by glial activation, pro-inflammatory cytokine release, and dysregulated neuroimmune signaling, constitute an additional target for therapeutic intervention [45]. Mitochondrial dysfunction and metabolic dysregulation contribute to fatigue, muscular pain, and cognitive impairment, while peripheral sensitization, including small fiber neuropathy, might drive widespread hyperalgesia in specific patient subsets [177]. Investigational pharmacologic agents, including glial modulators, ion channel regulators, neuroimmune signaling inhibitors, and metabolic enhancers, aim to correct these pathophysiological derangements [178]. Adjunctive neuromodulation strategies, including transcranial magnetic stimulation, transcutaneous electrical nerve stimulation, and vagus nerve stimulation, support mechanistically informed approaches to restore central pain circuitry and autonomic function [179,180].
Conversely, the incorporation of molecular, neuroimaging, and electrophysiological biomarkers into clinical trials holds considerable promise for improving the rigor and precision of therapeutic assessment. Biomarker-guided enrichment strategies can identify homogeneous patient cohorts, thereby improving signal detection in clinical trials and supporting mechanistic validation of novel interventions [181]. Biomarker-driven enrichment strategies can define mechanistically homogeneous patient cohorts, improving signal detection in trials and facilitating mechanistic validation of novel interventions [182]. When combined with patient-reported outcomes, objective physiological data facilitate a multidimensional framework for assessing treatment response, guiding individualized therapy adjustments, and refining predictive stratification models [183]. Such strategies adhere to the principles of precision medicine, focusing on targeted interventions customized to the biological and phenotypic characteristics of each patient.
Despite these advancements, significant barriers to clinical translation persist. Methodological heterogeneity, small sample sizes, and insufficient longitudinal validation restrict the applicability of candidate biomarkers and patient stratification algorithms [17].
High costs and technical complexity associated with molecular diagnostics and advanced neuroimaging restrict widespread accessibility, resulting in disparities in care [108]. Psychosocial factors, including variability in symptom expression, stigma, and clinician skepticism, further worsen diagnosis, patient engagement, and treatment adherence [184,185]. Ethical considerations related to predictive biomarker use, risk stratification, and equitable access to next-generation diagnostics and therapeutics necessitate careful attention to patient autonomy, consent, and equity in healthcare delivery [186]. Addressing these challenges requires multicenter, longitudinal studies, standardized measurement protocols, cost-effective diagnostic platforms, clinician education, and proactive patient engagement initiatives.
5. Conclusions
Fibromyalgia represents a paradigmatic nociplastic pain disorder, characterized by widespread musculoskeletal pain, debilitating fatigue, cognitive deficits, and autonomic imbalance, arising from interactions between central and peripheral neuroimmune, neuroendocrine, and metabolic mechanisms. Converging evidence from molecular, neuroimaging, and neurophysiological studies shows chronic low-grade neuroinflammation, maladaptive central sensitization, and dysregulated neurotransmission as pathophysiological substrates. Peripheral immune response, aberrant nociceptor excitability, and metabolic perturbations further contribute to symptom amplification and maintenance, establishing a bidirectional feed-forward loop between the periphery and CNS.
Advances in omics technologies, including metabolomics and transcriptomics, have elucidated disrupted energy metabolism, oxidative stress pathways, and neurotransmitter imbalances, enabling the identification of candidate molecular biomarkers for disease stratification and mechanistic insight. Neuroimaging modalities, such as fMRI, PET, DTI, and MRS, have consistently demonstrated functional and structural abnormalities in pain-processing networks, supporting the central sensitization model and revealing potential targets for therapeutic modulation. Additionally, wearable devices, ecological momentary assessment, and machine learning approaches have facilitated high-resolution, real-world characterization of symptom dynamics, highlighting the temporal variability, contextual sensitivity, and phenotypic heterogeneity inherent to fibromyalgia.
These findings underscore the shortcomings of symptom-based diagnostics and emphasize the need for integrative, multidimensional frameworks that incorporate molecular, neuroimaging, neurophysiological, and digital physiological monitoring data. Patient stratification based on mechanistic and phenotypic signatures holds significant potential for precision medicine, supporting targeted pharmacologic and non-pharmacologic interventions, optimized monitoring, and improved functional outcomes. Nevertheless, challenges including methodological heterogeneity, limited longitudinal validation, accessibility constraints, and ethical considerations must be addressed to translate these discoveries into routine clinical practice. In addition, substantial real-world barriers hinder implementation within healthcare systems, such as high economic costs, limited infrastructure and technological resources, restricted access in low-resource settings, and variable acceptability among patients and healthcare professionals due to concerns about usability, interpretability, training requirements, and clinical workload integration.
Collectively, the integration of multi-omics, neuroimaging, and digital phenotyping approaches constitutes a transformative paradigm for advancing fibromyalgia research and clinical management. Future efforts should focus on longitudinal, multimodal studies, mechanistically informed patient stratification, and personalized intervention strategies to reduce diagnostic delays, enhance treatment efficacy, and improve quality of life for individuals affected by this debilitating disorder. Equally important will be the development of scalable, cost-effective, and ethically robust implementation models that promote equitable access and facilitate clinical adoption, confirming that these innovations translate into sustainable, real-world healthcare solutions.
Funding
This research received no external funding.
Data Availability Statement
Not applicable. No new data were generated.
Conflicts of Interest
The author declares no conflict of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ACC | Anterior cingulate cortex |
| ANXA1 | Annexin A1 |
| ASICs | Acid-sensing ion channel |
| AXIN1 | Axis inhibition protein 1 |
| BBB | Blood–brain barrier |
| BCAA | Branched-chain amino acid |
| BDNF | Brain-derived neurotrophic factor |
| C16:0 | Ceramide with a 16-carbon fatty acid and 0 double bonds (palmitic acid) |
| C18:0 | Ceramide with an 18-carbon fatty acid and 0 double bonds (stearic acid) |
| C20:0 | Ceramide with a 20-carbon fatty acid and 0 double bonds (arachidic acid) |
| CAR | Cortisol awakening response |
| CBT | Cognitive-behavioral therapy |
| CCL11 | C-C motif chemokine ligand 11 |
| CCL17 | C-C motif chemokine ligand 17 |
| CCL2 | C-C motif chemokine ligand 2 |
| CCL5 | C-C motif chemokine ligand 5 |
| CD163 | Cluster of differentiation 163 |
| CNS | Central nervous system |
| COMT | Catechol-O-methyltransferase |
| COX | Cyclooxygenase |
| CPT1 | Carnitine palmitoyltransferase 1 |
| CRH | Corticotropin-releasing hormone |
| CRP | C-reactive protein |
| CSF | Cerebrospinal fluid |
| CX3CL1 | C-X3-C motif chemokine ligand 1 |
| CXCL10 | C-X-C motif chemokine ligand 10 |
| CXCL5 | C-X-C motif chemokine ligand 5 |
| CXCL8 | C-X-C motif chemokine ligand 8 |
| CXCL9 | C-X-C motif chemokine ligand 9 |
| CyB | Cytochrome b |
| DMN | Default mode network |
| DTI | Diffusion tensor imaging |
| EMA | Ecological momentary assessment |
| fMRI | Functional magnetic resonance imaging |
| GABA | Gamma-aminobutyric acid |
| GABRB3 | Gamma-aminobutyric acid type A receptor beta3 subunit |
| GEP | Graded exercise program |
| GPX | Glutathione peroxidase |
| GR | Glucocorticoid receptor |
| HO-1/HMOX1 | Heme oxygenase 1 |
| HPA | Hypothalamic–pituitary–adrenal axis |
| HRV | Heart rate variability |
| IBS | Irritable bowel syndrome |
| IFN-γ | Interferon gamma |
| IL-10 | Interleukin 10 |
| IL-17 | Interleukin 17 |
| IL-1β | Interleukin 1 beta |
| IL-6 | Interleukin 6 |
| IL-8 | Interleukin 8 |
| LDH | Lactate dehydrogenase |
| LOX | Lipoxygenase |
| LPC | Lysophosphatidylcholine |
| LPC 16:0 | Lysophosphatidylcholine with a 16-carbon fatty acid (palmitic acid) |
| LPC 18:0 | Lysophosphatidylcholine with an 18-carbon fatty acid (stearic acid) |
| MBSR | Mindfulness-based stress reduction |
| MDA | Malondialdehyde |
| ML | Machine learning |
| MRS | Magnetic resonance spectroscopy |
| mTOR | Mammalian target of rapamycin |
| MyD88 | Myeloid differentiation primary response 88 |
| ND4 | NADH dehydrogenase subunit 4 |
| NOS | Nitric oxide synthase |
| NQO1/NAD(P)H | Quinone dehydrogenase 1 |
| NR3C1 | Nuclear receptor subfamily 3 group C member 1 |
| NREM | Non-rapid eye movement |
| NRF-1 | Nuclear respiratory factor 1 |
| OSI | Oxidative stress index |
| P2X | Purinergic P2X receptors |
| P2Y | Purinergic P2Y receptors |
| PAG | Periaqueductal gray |
| PBMC | Peripheral blood mononuclear cell |
| PC | Phosphatidylcholine |
| PC 34:1 | Phosphatidylcholine with a total of 34 carbons in its two fatty acyl chains and 1 double bond |
| PC 36:2 | Phosphatidylcholine with 36 carbons in total and 2 double bonds |
| PET | Positron emission tomography |
| PFC | Prefrontal cortex |
| PGE2 | Prostaglandin E2 |
| QST | Quantitative sensory testing |
| REM | Rapid eye movement |
| ROS | Reactive oxygen species |
| S100A8 | S100 calcium-binding protein A8 |
| S100A9 | S100 calcium-binding protein A9 |
| SERPINA1 | Serpin family A member 1 |
| SIRT2 | Sirtuin 2 |
| SM | Sphingomyelin |
| SM d18:1/16:0 | Sphingomyelin with a sphingosine backbone of 18 carbons and 1 double bond + 16-carbon fatty acid (palmitic acid) |
| SM d18:1/18:0 | Sphingomyelin with a sphingosine backbone of 18:1 + 18-carbon fatty acid (stearic acid) |
| SNRI | Serotonin-norepinephrine reuptake inhibitor |
| SOCS3 | Suppressor of cytokine signaling 3 |
| SOD | Superoxide dismutase |
| STAMBP | STAM binding protein |
| TAS | Total antioxidant status |
| TCA | Tricarboxylic acid |
| Tfam | Mitochondrial transcription factor A |
| TGF-β | Transforming growth factor beta |
| TLR2 | Toll-like receptor 2 |
| TLR4 | Toll-like receptor 4 |
| TNF-α | Tumor necrosis factor alpha |
| TOS | Total oxidant status |
| TRPV | Transient receptor potential vanilloid |
| UCP2 | Uncoupling protein 2 |
| VBM | Voxel-based morphometry |
| VCAM1 | Vascular cell adhesion molecule 1 |
References
- Jurado-Priego, L.N.; Cueto-Ureña, C.; Ramírez-Expósito, M.J.; Martínez-Martos, J.M. Fibromyalgia: A Review of the Pathophysiological Mechanisms and Multidisciplinary Treatment Strategies. Biomedicines 2024, 12, 1543. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruschak, I.; Montesó-Curto, P.; Rosselló, L.; Aguilar Martín, C.; Sánchez-Montesó, L.; Toussaint, L. Fibromyalgia Syndrome Pain in Men and Women: A Scoping Review. Healthcare 2023, 11, 223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marques, A.P.; Santo, A.S.D.E.; Berssaneti, A.A.; Matsutani, L.A.; Yuan, S.L.K. Prevalence of fibromyalgia: Literature review update. Rev. Bras. Reumatol. Engl. Ed. 2017, 57, 356–363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sarzi-Puttini, P.; Giorgi, V.; Marotto, D.; Atzeni, F. Fibromyalgia: An update on clinical characteristics, aetiopathogenesis and treatment. Nat. Rev. Rheumatol. 2020, 16, 645–660. [Google Scholar] [CrossRef] [Scilit]
- Erdrich, S.; Harnett, J.E. Fibromyalgia severity and symptoms are associated with the disorders of gut-brain interaction. Eur. J. Pain 2025, 29, e4766. [Google Scholar] [CrossRef] [Scilit]
- Kulshreshtha, P.; Deepak, K.K. Autonomic nervous system profile in fibromyalgia patients and its modulation by exercise: A mini review. Clin. Physiol. Funct. Imaging 2013, 33, 83–91. [Google Scholar] [CrossRef] [Scilit]
- Vecchio, E.; Lombardi, R.; Paolini, M.; Libro, G.; Delussi, M.; Ricci, K.; Quitadamo, S.G.; Gentile, E.; Girolamo, F.; Iannone, F.; et al. Peripheral and central nervous system correlates in fibromyalgia. Eur. J. Pain 2020, 24, 1537–1547. [Google Scholar] [CrossRef] [Scilit]
- Mezhov, V.; Guymer, E.; Littlejohn, G. Central sensitivity and fibromyalgia. Intern. Med. J. 2021, 51, 1990–1998. [Google Scholar] [CrossRef] [Scilit]
- Bazzichi, L.; Giorgi, V.; Di Franco, M.; Iannuccelli, C.; Bongiovanni, S.; Batticciotto, A.; Pellegrino, G.; Sarzi Puttini, P. Environmental factors and fibromyalgia syndrome: A narrative review. Clin. Exp. Rheumatol. 2024, 42, 1240–1247. [Google Scholar]
- Mueller, C.; Fang, Y.D.; Jones, C.; McConathy, J.E.; Raman, F.; Lapi, S.E.; Younger, J.W. Evidence of neuroinflammation in fibromyalgia syndrome: A [18 F]DPA-714 positron emission tomography study. Pain 2023, 164, 2285–2295. [Google Scholar] [CrossRef] [Scilit]
- García-Domínguez, M. Fibromyalgia and Inflammation: Unrevealing the Connection. Cells 2025, 14, 271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Theoharides, T.C.; Tsilioni, I.; Bawazeer, M. Mast Cells, Neuroinflammation and Pain in Fibromyalgia Syndrome. Front. Cell Neurosci. 2019, 13, 353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Serra, J.; Collado, A.; Solà, R.; Antonelli, F.; Torres, X.; Salgueiro, M.; Quiles, C.; Bostock, H. Hyperexcitable C nociceptors in fibromyalgia. Ann. Neurol. 2014, 75, 196–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, W.N.; Lee, C.H.; Lin, S.H.; Wong, C.W.; Sun, W.H.; Wood, J.N.; Chen, C.C. Roles of ASIC3, TRPV1, and NaV1.8 in the transition from acute to chronic pain in a mouse model of fibromyalgia. Mol. Pain 2014, 10, 40. [Google Scholar] [CrossRef] [Scilit]
- Andrés-Rodríguez, L.; Borràs, X.; Feliu-Soler, A.; Pérez-Aranda, A.; Angarita-Osorio, N.; Moreno-Peral, P.; Montero-Marin, J.; García-Campayo, J.; Carvalho, A.F.; Maes, M.; et al. Peripheral immune aberrations in fibromyalgia: A systematic review, meta-analysis and meta-regression. Brain Behav. Immun. 2020, 87, 881–889. [Google Scholar] [CrossRef] [Scilit]
- Littlejohn, G.; Guymer, E. Neurogenic inflammation in fibromyalgia. Semin. Immunopathol. 2018, 40, 291–300. [Google Scholar] [CrossRef] [Scilit]
- Hackshaw, K.V. The Search for Biomarkers in Fibromyalgia. Diagnostics 2021, 11, 156. [Google Scholar] [CrossRef] [Scilit]
- Benjamin, N.Z.Y.; Parekh, R.S.; Inban, P.; Sakthi, S.; Tekuru, Y.; Prajjwal, P.; John, J.; Sharma, R. Fibromyalgia: Advances in pathophysiology, diagnostic biomarkers, genetic insights, multisystemic involvement, and treatment updates and multidisciplinary interventions. Dis. Mon. 2025, 71, 101965. [Google Scholar] [CrossRef] [Scilit]
- Salemi, S.; Rethage, J.; Wollina, U.; Michel, B.A.; Gay, R.E.; Gay, S.; Sprott, H. Detection of interleukin 1beta (IL-1beta), IL-6, and tumor necrosis factor-alpha in skin of patients with fibromyalgia. J. Rheumatol. 2003, 30, 146–150. [Google Scholar]
- Kadetoff, D.; Lampa, J.; Westman, M.; Andersson, M.; Kosek, E. Evidence of central inflammation in fibromyalgia—Increased cerebrospinal fluid interleukin-8 levels. J. Neuroimmunol. 2012, 242, 33–38. [Google Scholar] [CrossRef] [Scilit]
- Kosek, E.; Altawil, R.; Kadetoff, D.; Finn, A.; Westman, M.; Le Maître, E.; Andersson, M.; Jensen-Urstad, M.; Lampa, J. Evidence of different mediators of central inflammation in dysfunctional and inflammatory pain—Interleukin-8 in fibromyalgia and interleukin-1β in rheumatoid arthritis. J. Neuroimmunol. 2015, 280, 49–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bäckryd, E.; Tanum, L.; Lind, A.L.; Larsson, A.; Gordh, T. Evidence of both systemic inflammation and neuroinflammation in fibromyalgia patients, as assessed by a multiplex protein panel applied to the cerebrospinal fluid and to plasma. J. Pain Res. 2017, 10, 515–525. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bäckryd, E.; Lind, A.L.; Thulin, M.; Larsson, A.; Gerdle, B.; Gordh, T. High levels of cerebrospinal fluid chemokines point to the presence of neuroinflammation in peripheral neuropathic pain: A cross-sectional study of 2 cohorts of patients compared with healthy controls. Pain 2017, 158, 2487–2495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bazzichi, L.; Rossi, A.; Massimetti, G.; Giannaccini, G.; Giuliano, T.; De Feo, F.; Ciapparelli, A.; Dell’Osso, L.; Bombardieri, S. Cytokine patterns in fibromyalgia and their correlation with clinical manifestations. Clin. Exp. Rheumatol. 2007, 25, 225–230. [Google Scholar]
- Delay, M.; Macian, N.; Dualé, C.; Pereira, B.; Aissouni, Y.; Lippi, Y.; Pickering, G. Two epigenetic markers of the fibromyalgia syndrome: A matched case-control study. J. Pain 2025, 39, 105630. [Google Scholar] [CrossRef] [Scilit]
- Becker, S.; Schweinhardt, P. Dysfunctional neurotransmitter systems in fibromyalgia, their role in central stress circuitry and pharmacological actions on these systems. Pain Res. Treat. 2012, 2012, 741746. [Google Scholar] [CrossRef] [Scilit]
- López-Solà, M.; Woo, C.W.; Pujol, J.; Deus, J.; Harrison, B.J.; Monfort, J.; Wager, T.D. Towards a neurophysiological signature for fibromyalgia. Pain 2017, 158, 34–47. [Google Scholar] [CrossRef] [Scilit]
- Aster, H.C.; Evdokimov, D.; Braun, A.; Üçeyler, N.; Kampf, T.; Pham, M.; Homola, G.A.; Sommer, C. CNS imaging characteristics in fibromyalgia patients with and without peripheral nerve involvement. Sci. Rep. 2022, 12, 6707. [Google Scholar] [CrossRef] [Scilit]
- Tu, Y.; Wang, J.; Xiong, F.; Gao, F. Disrupted white matter microstructure in patients with fibromyalgia owing predominantly to psychological factors: A diffusion tensor imaging study. Pain Physician 2022, 25, E1305–E1313. [Google Scholar]
- Albrecht, D.S.; Forsberg, A.; Sandström, A.; Bergan, C.; Kadetoff, D.; Protsenko, E.; Lampa, J.; Lee, Y.C.; Höglund, C.O.; Catana, C.; et al. Brain glial activation in fibromyalgia—A multi-site positron emission tomography investigation. Brain Behav. Immun. 2019, 75, 72–83. [Google Scholar] [CrossRef] [Scilit]
- Carneiro, A.M.; de Góes Salvetti, M.; Dale, C.S.; da Silva, V.A. Quantitative Sensory Testing in Fibromyalgia Syndrome: A Scoping Review. Biomedicines 2025, 13, 988. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de la Coba, P.; Montoro, C.I.; Reyes Del Paso, G.A.; Galvez-Sánchez, C.M. Algometry for the assessment of central sensitisation to pain in fibromyalgia patients: A systematic review. Ann. Med. 2022, 54, 1403–1422. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evdokimov, D.; Frank, J.; Klitsch, A.; Unterecker, S.; Warrings, B.; Serra, J.; Papagianni, A.; Saffer, N.; Meyer Zu Altenschildesche, C.; Kampik, D.; et al. Reduction of skin innervation is associated with a severe fibromyalgia phenotype. Ann. Neurol. 2019, 86, 504–516. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khoonsari, P.E.; Musunri, S.; Herman, S.; Svensson, C.I.; Tanum, L.; Gordh, T.; Kultima, K. Systematic analysis of the cerebrospinal fluid proteome of fibromyalgia patients. J. Proteom. 2019, 190, 35–43. [Google Scholar] [CrossRef] [Scilit]
- Ernberg, M.; Christidis, N.; Ghafouri, B.; Bileviciute-Ljungar, I.; Löfgren, M.; Bjersing, J.; Palstam, A.; Larsson, A.; Mannerkorpi, K.; Gerdle, B.; et al. Plasma cytokine levels in fibromyalgia and their response to 15 weeks of progressive resistance exercise or relaxation therapy. Mediat. Inflamm. 2018, 2018, 3985154. [Google Scholar] [CrossRef] [Scilit]
- Shkundin, A.; Halaris, A. IL-8 (CXCL8) correlations with psychoneuroimmunological processes and neuropsychiatric conditions. J. Pers. Med. 2024, 14, 488. [Google Scholar] [CrossRef] [Scilit]
- Giron, S.E.; Bjurstrom, M.F.; Griffis, C.A.; Ferrante, F.M.; Wu, I.I.; Nicol, A.L.; Grogan, T.R.; Burkard, J.F.; Irwin, M.R.; Breen, E.C. Increased central nervous system interleukin-8 in a majority postlaminectomy syndrome chronic pain population. Pain Med. 2018, 19, 1033–1043. [Google Scholar] [CrossRef] [Scilit]
- Larson, A.A.; Giovengo, S.L.; Russell, J.I.; Michalek, J.E. Changes in the concentrations of amino acids in the cerebrospinal fluid that correlate with pain in patients with fibromyalgia: Implications for nitric oxide pathways. Pain 2000, 87, 201–211. [Google Scholar] [CrossRef] [Scilit]
- Gkouvi, A.; Tsiogkas, S.G.; Bogdanos, D.P.; Gika, H.; Goulis, D.G.; Grammatikopoulou, M.G. Proteomics in patients with fibromyalgia syndrome: A systematic review of observational studies. Curr. Pain Headache Rep. 2024, 28, 565–586. [Google Scholar] [CrossRef] [Scilit]
- Ruggieri, M.; Paparella, G.; Clemente, L.; Libro, G.; Gargano, C.D.; de Tommaso, M. Plasma neurofilament light chain in fibromyalgia: A case control study exploring correlation with clinical and cognitive features. Eur. J. Pain 2025, 29, e4752. [Google Scholar] [CrossRef] [Scilit]
- Laske, C.; Stransky, E.; Eschweiler, G.W.; Klein, R.; Wittorf, A.; Leyhe, T.; Richartz, E.; Köhler, N.; Bartels, M.; Buchkremer, G.; et al. Increased BDNF serum concentration in fibromyalgia with or without depression or antidepressants. J. Psychiatr. Res. 2007, 41, 600–605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russell, I.J.; Orr, M.D.; Littman, B.; Vipraio, G.A.; Alboukrek, D.; Michalek, J.E.; Lopez, Y.; MacKillip, F. Elevated cerebrospinal fluid levels of substance P in patients with the fibromyalgia syndrome. Arthritis Rheum. 1994, 37, 1593–1601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giovengo, S.L.; Russell, I.J.; Larson, A.A. Increased concentrations of nerve growth factor in cerebrospinal fluid of patients with fibromyalgia. J. Rheumatol. 1999, 26, 1564–1569. [Google Scholar] [PubMed]
- Gigase, F.A.J.; Smith, E.; Collins, B.; Moore, K.; Snijders, G.J.L.J.; Katz, D.; Bergink, V.; Perez-Rodriquez, M.M.; De Witte, L.D. The association between inflammatory markers in blood and cerebrospinal fluid: A systematic review and meta-analysis. Mol. Psychiatry 2023, 28, 1502–1515. [Google Scholar] [CrossRef] [Scilit]
- Findeisen, K.; Guymer, E.; Littlejohn, G. Neuroinflammatory and immunological aspects of fibromyalgia. Brain Sci. 2025, 15, 206. [Google Scholar] [CrossRef] [Scilit]
- O’Mahony, L.F.; Srivastava, A.; Mehta, P.; Ciurtin, C. Is fibromyalgia associated with a unique cytokine profile? A systematic review and meta-analysis. Rheumatology 2021, 60, 2602–2614. [Google Scholar] [CrossRef] [Scilit]
- Ji, R.R.; Xu, Z.Z.; Gao, Y.J. Emerging targets in neuroinflammation-driven chronic pain. Nat. Rev. Drug Discov. 2014, 13, 533–548. [Google Scholar] [CrossRef] [Scilit]
- Zetterman, T.; Markkula, R.; Kalso, E. Elevated highly sensitive C-reactive protein in fibromyalgia associates with symptom severity. Rheumatol. Adv. Pract. 2022, 6, rkac053. [Google Scholar] [CrossRef] [Scilit]
- Fineschi, S.; Klar, J.; Gustafsson, K.A.; Jonsson, K.; Karlsson, B.; Dahl, N. Inflammation and interferon signatures in peripheral B-lymphocytes and sera of individuals with fibromyalgia. Front. Immunol. 2022, 13, 874490. [Google Scholar] [CrossRef] [Scilit]
- Banks, W.A. The blood–brain barrier in neuroimmunology: Tales of separation and assimilation. Brain Behav. Immun. 2015, 44, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Gerdle, B.; Wåhlén, K.; Gordh, T.; Bäckryd, E.; Carlsson, A.; Ghafouri, B. Plasma proteins from several components of the immune system differentiate chronic widespread pain patients from healthy controls—An exploratory case-control study combining targeted and non-targeted protein identification. Medicine 2022, 101, e31013. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beiner, E.; Lucas, V.; Reichert, J.; Buhai, D.V.; Jesinghaus, M.; Vock, S.; Drusko, A.; Baumeister, D.; Eich, W.; Friederich, H.C.; et al. Stress biomarkers in individuals with fibromyalgia syndrome: A systematic review with meta-analysis. Pain 2023, 164, 1416–1427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weissbecker, I.; Floyd, A.; Dedert, E.; Salmon, P.; Sephton, S. Childhood trauma and diurnal cortisol disruption in fibromyalgia syndrome. Psychoneuroendocrinology 2006, 31, 312–324. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McLean, S.A.; Williams, D.A.; Harris, R.E.; Kop, W.J.; Groner, K.H.; Ambrose, K.; Lyden, A.K.; Gracely, R.H.; Crofford, L.J.; Geisser, M.E.; et al. Momentary relationship between cortisol secretion and symptoms in patients with fibromyalgia. Arthritis Rheum. 2005, 52, 3660–3669. [Google Scholar] [CrossRef] [Scilit]
- Riva, R.; Mork, P.J.; Westgaard, R.H.; Lundberg, U. Comparison of the cortisol awakening response in women with shoulder and neck pain and women with fibromyalgia. Psychoneuroendocrinology 2012, 37, 299–306. [Google Scholar] [CrossRef] [Scilit]
- Fatima, G.; Das, S.K.; Mahdi, A.A.; Verma, N.S.; Khan, F.H.; Tiwari, A.M.; Jafer, T.; Anjum, B. Circadian rhythm of serum cortisol in female patients with fibromyalgia syndrome. Indian J. Clin. Biochem. 2013, 28, 181–184. [Google Scholar] [CrossRef] [Scilit]
- Beiner, E.; Hermes, M.; Reichert, J.; Kleinke, K.; Vock, S.; Löffler, A.; Ader, L.; Sirazitdinov, A.; Keil, S.; Schmidt, T.; et al. Perceived and endocrine acute and chronic stress indicators in fibromyalgia syndrome. Sci. Rep. 2024, 14, 30471. [Google Scholar] [CrossRef] [Scilit]
- Riva, R.; Mork, P.J.; Westgaard, R.H.; Rø, M.; Lundberg, U. Fibromyalgia syndrome is associated with hypocortisolism. Int. J. Behav. Med. 2010, 17, 223–233. [Google Scholar] [CrossRef] [Scilit]
- Lin, Y.-J.; Ko, Y.C.; Chow, L.H.; Hsiao, F.J.; Liu, H.Y.; Wang, P.N.; Chen, W.T. Salivary cortisol is associated with cognitive changes in patients with fibromyalgia. Sci. Rep. 2021, 11, 1311. [Google Scholar] [CrossRef] [Scilit]
- Wingenfeld, K.; Nutzinger, D.; Kauth, J.; Hellhammer, D.H.; Lautenbacher, S. Salivary cortisol release and hypothalamic–pituitary–adrenal axis feedback sensitivity in fibromyalgia is associated with depression but not with pain. J. Pain 2010, 11, 1195–1208. [Google Scholar] [CrossRef] [Scilit]
- Izquierdo-Alvarez, S.; Bocos-Terraz, J.P.; Bancalero-Flores, J.L.; Pavón-Romero, L.; Serrano-Ostariz, E.; de Miquel, C.A. Is there an association between fibromyalgia and below-normal levels of urinary cortisol? BMC Res. Notes 2008, 1, 134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsilioni, I.; Russell, I.J.; Stewart, J.M.; Gleason, R.M.; Theoharides, T.C. Neuropeptides CRH, SP, HK-1, and inflammatory cytokines IL-6 and TNF are increased in serum of patients with fibromyalgia syndrome, implicating mast cells. J. Pharmacol. Exp. Ther. 2016, 356, 664–672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McLean, S.A.; Williams, D.A.; Stein, P.K.; Harris, R.E.; Lyden, A.K.; Whalen, G.; Park, K.M.; Liberzon, I.; Sen, A.; Gracely, R.H.; et al. Cerebrospinal fluid corticotropin-releasing factor concentration is associated with pain but not fatigue symptoms in patients with fibromyalgia. Neuropsychopharmacology 2006, 31, 2776–2782. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gupta, A.; Silman, A.J. Psychological stress and fibromyalgia: A review of the evidence suggesting a neuroendocrine link. Arthritis Res. Ther. 2004, 6, 98–106. [Google Scholar] [CrossRef] [Scilit]
- Geiss, A.; Rohleder, N.; Anton, F. Evidence for an association between an enhanced reactivity of interleukin-6 levels and reduced glucocorticoid sensitivity in patients with fibromyalgia. Psychoneuroendocrinology 2012, 37, 671–684. [Google Scholar] [CrossRef] [Scilit]
- Light, K.C.; White, A.T.; Tadler, S.; Iacob, E.; Light, A.R. Genetics and gene expression involving stress and distress pathways in fibromyalgia with and without comorbid chronic fatigue syndrome. Pain Res. Treat. 2012, 2012, 427869. [Google Scholar] [CrossRef] [Scilit]
- Gerra, M.C.; Carnevali, D.; Ossola, P.; González-Villar, A.; Pedersen, I.S.; Triñanes, Y.; Donnini, C.; Manfredini, M.; Arendt-Nielsen, L.; Carrillo-de-la-Peña, M.T. DNA methylation changes in fibromyalgia suggest the role of the immune-inflammatory response and central sensitization. J. Clin. Med. 2021, 10, 4992. [Google Scholar] [CrossRef] [Scilit]
- Kang, J.H.; Kim, J.K.; Hong, S.H.; Lee, C.H.; Choi, B.Y. Heart rate variability for quantification of autonomic dysfunction in fibromyalgia. Ann. Rehabil. Med. 2016, 40, 301–309. [Google Scholar] [CrossRef] [Scilit]
- Zetterman, T.; Markkula, R.; Miettinen, T.; Kalso, E. Heart rate variability responses to cognitive stress in fibromyalgia are characterised by inadequate autonomous system stress responses: A clinical trial. Sci. Rep. 2023, 13, 700. [Google Scholar] [CrossRef] [Scilit]
- Kocyigit, B.F.; Akyol, A. Coexistence of fibromyalgia syndrome and inflammatory rheumatic diseases, and autonomic cardiovascular system involvement in fibromyalgia syndrome. Clin. Rheumatol. 2023, 42, 645–652. [Google Scholar] [CrossRef] [Scilit]
- Riva, R.; Mork, P.J.; Westgaard, R.H.; Okkenhaug Johansen, T.; Lundberg, U. Catecholamines and heart rate in female fibromyalgia patients. J. Psychosom. Res. 2012, 72, 51–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russell, I.J.; Vaeroy, H.; Javors, M.; Nyberg, F. Cerebrospinal fluid biogenic amine metabolites in fibromyalgia/fibrositis syndrome and rheumatoid arthritis. Arthritis Rheum. 1992, 35, 550–556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Light, K.C.; Bragdon, E.E.; Grewen, K.M.; Brownley, K.A.; Girdler, S.S.; Maixner, W. Adrenergic dysregulation and pain with and without acute beta-blockade in women with fibromyalgia and temporomandibular disorder. J. Pain 2009, 10, 542–552. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martínez-Jauand, M.; Sitges, C.; Rodríguez, V.; Picornell, A.; Ramon, M.; Buskila, D.; Montoya, P. Pain sensitivity in fibromyalgia is associated with catechol-O-methyltransferase (COMT) gene. Eur. J. Pain 2013, 17, 16–27. [Google Scholar] [CrossRef] [Scilit]
- Zamunér, A.R.; Porta, A.; Andrade, C.P.; Forti, M.; Marchi, A.; Furlan, R.; Barbic, F.; Catai, A.M.; Silva, E. The degree of cardiac baroreflex involvement during active standing is associated with the quality of life in fibromyalgia patients. PLoS ONE 2017, 12, e0179500. [Google Scholar] [CrossRef] [Scilit]
- Reyes Del Paso, G.A.; Contreras-Merino, A.M.; de la Coba, P.; Duschek, S. The cardiac, vasomotor, and myocardial branches of the baroreflex in fibromyalgia: Associations with pain, affective impairments, sleep problems, and fatigue. Psychophysiology 2021, 58, e13800. [Google Scholar] [CrossRef] [Scilit]
- Pernambuco, A.P.; Schetino, L.P.; Viana, R.S.; Carvalho, L.S.; d’Ávila Reis, D. The involvement of melatonin in the clinical status of patients with fibromyalgia syndrome. Clin. Exp. Rheumatol. 2015, 33, S14–S19. [Google Scholar]
- Caumo, W.; Hidalgo, M.P.; Souza, A.; Torres, I.L.S.; Antunes, L.C. Melatonin is a biomarker of circadian dysregulation and is correlated with major depression and fibromyalgia symptom severity. J. Pain Res. 2019, 12, 545–556. [Google Scholar] [CrossRef] [Scilit]
- Piras, C.; Pibiri, M.; Conte, S.; Ferranti, G.; Leoni, V.P.; Liggi, S.; Spada, M.; Muntoni, S.; Caboni, P.; Atzori, L. Metabolomics analysis of plasma samples of patients with fibromyalgia and electromagnetic sensitivity using GC-MS technique. Sci. Rep. 2022, 12, 21923. [Google Scholar] [CrossRef] [Scilit]
- Mohapatra, G.; Dachet, F.; Coleman, L.J.; Gillis, B.; Behm, F.G. Identification of unique genomic signatures in patients with fibromyalgia and chronic pain. Sci. Rep. 2024, 14, 3949. [Google Scholar] [CrossRef] [Scilit]
- Rus, A.; López-Sánchez, J.A.; Martínez-Martos, J.M.; Ramírez-Expósito, M.J.; Molina, F.; Correa-Rodríguez, M.; Aguilar-Ferrándiz, M.E. Predictive ability of serum amino acid levels to differentiate fibromyalgia patients from healthy subjects. Mol. Diagn. Ther. 2024, 28, 113–128. [Google Scholar] [CrossRef] [Scilit]
- Maes, M.; Verkerk, R.; Delmeire, L.; Van Gastel, A.; van Hunsel, F.; Scharpé, S. Serotonergic markers and lowered plasma branched-chain amino acid concentrations in fibromyalgia. Psychiatry Res. 2000, 97, 11–20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Satis, S. Amino acid levels in patients with fibromyalgia syndrome: Amino acid and fibromyalgia. Chron. Precis. Med. Res. 2024, 5, 89–93. [Google Scholar]
- Schwarz, M.J.; Offenbaecher, M.; Neumeister, A.; Ewert, T.; Willeit, M.; Praschak-Rieder, N.; Zach, J.; Zacherl, M.; Lossau, K.; Weisser, R.; et al. Evidence for an altered tryptophan metabolism in fibromyalgia. Neurobiol. Dis. 2002, 11, 434–442. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Groven, N.; Reitan, S.K.; Fors, E.A.; Guzey, I.C. Kynurenine metabolites and ratios differ between chronic fatigue syndrome, fibromyalgia, and healthy controls. Psychoneuroendocrinology 2021, 131, 105287. [Google Scholar] [CrossRef] [Scilit]
- Fayed, N.; Garcia-Campayo, J.; Magallón, R.; Andrés-Bergareche, H.; Luciano, J.V.; Andres, E.; Beltrán, J. Localized 1H-NMR spectroscopy in patients with fibromyalgia: A controlled study of changes in cerebral glutamate/glutamine, inositol, choline, and N-acetylaspartate. Arthritis Res. Ther. 2010, 12, R134. [Google Scholar] [CrossRef] [Scilit]
- Cimen, O.B.; Cimen, M.Y.; Yapici, Y.; Camdeviren, H. Arginase, NOS activities, and clinical features in fibromyalgia patients. Pain Med. 2009, 10, 813–818. [Google Scholar] [CrossRef] [Scilit]
- Jakobsson, J.E.; Menezes, J.; Krock, E.; Hunt, M.A.; Carlsson, H.; Vaivade, A.; Emami Khoonsari, P.; Agalave, N.M.; Sandström, A.; Kadetoff, D.; et al. Fibromyalgia patients have altered lipid concentrations associated with disease symptom severity and anti-satellite glial cell IgG antibodies. J. Pain 2025, 29, 105331. [Google Scholar] [CrossRef] [Scilit]
- Uslu, E.Y.; Uslu, M.F.; Yıldız, S.; Tabara, M.F. Evaluating oxidative stress in fibromyalgia: Diagnostic utility and its relationship with clinical and psychological parameters. Medicina 2025, 61, 1248. [Google Scholar] [CrossRef] [Scilit]
- Rossini, M.; Di Munno, O.; Valentini, G.; Bianchi, G.; Biasi, G.; Cacace, E.; Malesci, D.; La Montagna, G.; Viapiana, O.; Adami, S. Double-blind, multicenter trial comparing acetyl L-carnitine with placebo in the treatment of fibromyalgia patients. Clin. Exp. Rheumatol. 2007, 25, 182–188. [Google Scholar]
- Hong, M.; Wang, J.; Huang, X.; Xu, Q.; Xiao, Y.; Ling, K. Carnitine and other metabolites in fibromyalgia: A clinical perspective on a Mendelian randomization study. J. Pain Res. 2025, 18, 7097–7107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ardiç, F.; Ozgen, M.; Aybek, H.; Rota, S.; Cubukçu, D.; Gökgöz, A. Effects of balneotherapy on serum IL-1, PGE2 and LTB4 levels in fibromyalgia patients. Rheumatol. Int. 2007, 27, 441–446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fais, A.; Cacace, E.; Corda, M.; Era, B.; Peri, M.; Utzeri, S.; Ruggiero, V. Purine metabolites in fibromyalgia syndrome. Clin. Biochem. 2013, 46, 37–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zetterman, T.; Nieminen, A.I.; Markkula, R.; Kalso, E.; Lötsch, J. Machine learning identifies fatigue as a key symptom of fibromyalgia reflected in tyrosine, purine, pyrimidine, and glutaminergic metabolism. Clin. Transl. Sci. 2024, 17, e13740. [Google Scholar] [CrossRef] [Scilit]
- Menzies, V.; Starkweather, A.; Yao, Y.; Thacker, L.R., II; Garrett, T.J.; Swift-Scanlan, T.; Kelly, D.L.; Patel, P.; Lyon, D.E. Metabolomic differentials in women with and without fibromyalgia. Clin. Transl. Sci. 2020, 13, 67–77. [Google Scholar] [CrossRef] [Scilit]
- Jung, Y.H.; Kim, H.; Lee, D.; Lee, J.Y.; Moon, J.Y.; Choi, S.H.; Kang, D.H. Dysfunctional energy metabolisms in fibromyalgia compared with healthy subjects. Mol. Pain 2021, 17, 17448069211012833. [Google Scholar] [CrossRef] [Scilit]
- Jones, K.D.; Gelbart, T.; Whisenant, T.C.; Waalen, J.; Mondala, T.S.; Iklé, D.N.; Salomon, D.R.; Bennett, R.M.; Kurian, S.M. Genome-wide expression profiling in the peripheral blood of patients with fibromyalgia. Clin. Exp. Rheumatol. 2016, 34, S89–S98. [Google Scholar]
- Lai, P.-C.; Yen, C.-M.; Lin, M.-C.; Chen, Y.-H.; Liao, H.-Y.; Huang, Y.-W.; Lin, Y.-W. Electroacupuncture Attenuates Fibromyalgia Pain via Toll-like Receptor 4 in the Mouse Brain. Life 2023, 13, 1160. [Google Scholar] [CrossRef] [Scilit]
- Hsiao, I.-H.; Lin, M.-C.; Hsu, H.-C.; Chae, Y.; Lin, I.-Y.; Lin, Y.-W. Electroacupuncture Relieves Fibromyalgia Pain in a Female Mouse Model by Augmenting Cannabinoid Receptor 1 Expression and Suppressing Astrocyte and Microglial Activation in Nociceptive Pathways. Biomedicines 2025, 13, 2112. [Google Scholar] [CrossRef] [Scilit]
- Marino, Y.; Inferrera, F.; D’Amico, R.; Impellizzeri, D.; Cordaro, M.; Siracusa, R.; Gugliandolo, E.; Fusco, R.; Cuzzocrea, S.; Di Paola, R. Role of mitochondrial dysfunction and biogenesis in fibromyalgia syndrome: Molecular mechanism in central nervous system. Biochim. Biophys. Acta Mol. Basis Dis. 2024, 1870, 167301. [Google Scholar] [CrossRef] [Scilit]
- Macchi, C.; Giachi, A.; Fichtner, I.; Pedretti, S.; Sarzi-Puttini, P.; Mitro, N.; Corsini, A.; Ruscica, M.; Gualtierotti, R. Mitochondrial function in patients affected with fibromyalgia syndrome is impaired and correlates with disease severity. Sci. Rep. 2024, 14, 30247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, L.; Higgs, M.; Snaith, A.; Lodge, T.A.; Strong, J.; Espejo-Oltra, J.A.; Kujawski, S.; Zalewski, P.; Pretorius, E.; Hoerger, M.; et al. Dysregulation of lipid metabolism, energy production, and oxidative stress in myalgic encephalomyelitis/chronic fatigue syndrome, Gulf War Syndrome and fibromyalgia. Front. Neurosci. 2025, 19, 1498981. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ho, T.; Ryan, M.; Holle, J. Redox reactions in chronic pain: Mechanisms and relevance in fibromyalgia. Front. Pain Res. 2025, 6, 1593908. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, S.B.; Maixner, D.W.; Fillingim, R.B.; Slade, G.; Gracely, R.H.; Ambrose, K.; Zaykin, D.V.; Hyde, C.; John, S.; Tan, K.; et al. Large candidate gene association study reveals genetic risk factors and therapeutic targets for fibromyalgia. Arthritis Rheum. 2012, 64, 584–593. [Google Scholar] [CrossRef] [Scilit]
- Ovrom, E.A.; Mostert, K.A.; Khakhkhar, S.; McKee, D.P.; Yang, P.; Her, Y.F. A Comprehensive Review of the Genetic and Epigenetic Contributions to the Development of Fibromyalgia. Biomedicines 2023, 11, 1119. [Google Scholar] [CrossRef] [Scilit]
- Bonomi, S.; Oltra, E.; Alberio, T. In Search of Molecular Correlates of Fibromyalgia: The Quest for Objective Diagnosis and Effective Treatments. Int. J. Mol. Sci. 2025, 26, 9762. [Google Scholar] [CrossRef] [Scilit]
- Diatchenko, L.; Fillingim, R.B.; Smith, S.B.; Maixner, W. The phenotypic and genetic signatures of common musculoskeletal pain conditions. Nat. Rev. Rheumatol. 2013, 9, 340–350. [Google Scholar] [CrossRef] [Scilit]
- Mackey, S.; Aghaeepour, N.; Gaudilliere, B.; Kao, M.C.; Kaptan, M.; Lannon, E.; Pfyffer, D.; Weber, K. Innovations in acute and chronic pain biomarkers: Enhancing diagnosis and personalized therapy. Reg. Anesth. Pain Med. 2025, 50, 110–120. [Google Scholar] [CrossRef] [Scilit]
- Curatolo, M.; Chiu, A.P.; Chia, C.; Ward, A.; Khan, S.; Johnston, S.K.; Klein, R.M.; Henze, D.A.; Zhu, W.; Raftery, D. Multi-omics profiles of chronic low back pain and fibromyalgia—Study protocol. PLoS ONE 2025, 20, e0312061. [Google Scholar] [CrossRef] [Scilit]
- Durán-González, E.; Ramírez-Tejero, J.A.; Pérez-Sánchez, M.; Morales-Torres, C.; Gómez-Morano, R.; Díaz-López, C.; Martínez-Lara, A.; Cotán, D. Fibromyalgia diagnosis from a multi-omics approach: A gut feeling. Front. Microbiol. 2025, 16, 1641185. [Google Scholar] [CrossRef] [Scilit]
- Cagnie, B.; Coppieters, I.; Denecker, S.; Six, J.; Danneels, L.; Meeus, M. Central sensitization in fibromyalgia? A systematic review on structural and functional brain MRI. Semin. Arthritis Rheum. 2014, 44, 68–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Müller, M.; Wüthrich, F.; Federspiel, A.; Wiest, R.; Egloff, N.; Reichenbach, S.; Exadaktylos, A.; Jüni, P.; Curatolo, M.; Walther, S. Altered central pain processing in fibromyalgia—A multimodal neuroimaging case-control study using arterial spin labelling. PLoS ONE 2021, 16, e0235879. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.; Loggia, M.L.; Cahalan, C.M.; Harris, R.E.; Beissner, F.; Garcia, R.G.; Kim, H.; Wasan, A.D.; Edwards, R.R.; Napadow, V. The somatosensory link in fibromyalgia: Functional connectivity of the primary somatosensory cortex is altered by sustained pain and is associated with clinical/autonomic dysfunction. Arthritis Rheumatol. 2015, 67, 1395–1405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sluka, K.A.; Clauw, D.J. Neurobiology of fibromyalgia and chronic widespread pain. Neuroscience 2016, 338, 114–129. [Google Scholar] [CrossRef] [Scilit]
- Hsiao, F.J.; Wang, S.J.; Lin, Y.Y.; Fuh, J.L.; Ko, Y.C.; Wang, P.N.; Chen, W.T. Altered insula-default mode network connectivity in fibromyalgia: A resting-state magnetoencephalographic study. J. Headache Pain 2017, 18, 89. [Google Scholar] [CrossRef] [Scilit]
- Liu, A.; Jiang, H.; Li, Y.; Jiang, Z.; Huang, S.; Ying, Z. Altered whole brain functional activity in patients with fibromyalgia. Clin. Exp. Rheumatol. 2024, 42, 1164–1169. [Google Scholar] [CrossRef] [Scilit]
- Harper, D.E.; Ichesco, E.; Schrepf, A.; Hampson, J.P.; Clauw, D.J.; Schmidt-Wilcke, T.; Harris, R.E.; Harte, S.E. Resting functional connectivity of the periaqueductal gray is associated with normal inhibition and pathological facilitation in conditioned pain modulation. J. Pain 2018, 19, 635.e1–635.e15. [Google Scholar] [CrossRef] [Scilit]
- Mosch, B.; Hagena, V.; Herpertz, S.; Ruttorf, M.; Diers, M. Neural correlates of control over pain in fibromyalgia patients. Neuroimage Clin. 2023, 37, 103355. [Google Scholar] [CrossRef] [Scilit]
- Fallon, N.; Chiu, Y.; Nurmikko, T.; Stancak, A. Functional connectivity with the default mode network is altered in fibromyalgia patients. PLoS ONE 2016, 11, e0159198. [Google Scholar] [CrossRef] [Scilit]
- Čeko, M.; Frangos, E.; Gracely, J.; Richards, E.; Wang, B.; Schweinhardt, P.; Bushnell, M.C. Default mode network changes in fibromyalgia patients are largely dependent on current clinical pain. Neuroimage 2020, 216, 116877. [Google Scholar] [CrossRef] [Scilit]
- Kong, J.; Wolcott, E.; Wang, Z.; Jorgenson, K.; Harvey, W.F.; Tao, J.; Rones, R.; Wang, C. Altered resting state functional connectivity of the cognitive control network in fibromyalgia and the modulation effect of mind-body intervention. Brain Imaging Behav. 2019, 13, 482–492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ichesco, E.; Schmidt-Wilcke, T.; Bhavsar, R.; Clauw, D.J.; Peltier, S.J.; Kim, J.; Napadow, V.; Hampson, J.P.; Kairys, A.E.; Williams, D.A.; et al. Altered resting state connectivity of the insular cortex in individuals with fibromyalgia. J. Pain 2014, 15, 815–826.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Robinson, M.E.; Craggs, J.G.; Price, D.D.; Perlstein, W.M.; Staud, R. Gray matter volumes of pain-related brain areas are decreased in fibromyalgia syndrome. J. Pain 2011, 12, 436–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, C.; Lee, S.H.; Weng, H.H. Gray matter atrophy within the default mode network of fibromyalgia: A meta-analysis of voxel-based morphometry studies. Biomed. Res. Int. 2016, 2016, 7296125. [Google Scholar] [CrossRef] [Scilit]
- Henn, A.T.; Larsen, B.; Frahm, L.; Xu, A.; Adebimpe, A.; Scott, J.C.; Linguiti, S.; Sharma, V.; Basbaum, A.I.; Corder, G.; et al. Structural imaging studies of patients with chronic pain: An anatomical likelihood estimate meta-analysis. Pain 2023, 164, e10–e24. [Google Scholar] [CrossRef] [Scilit]
- Mosch, B.; Hagena, V.; Herpertz, S.; Diers, M. Brain morphometric changes in fibromyalgia and the impact of psychometric and clinical factors: A volumetric and diffusion-tensor imaging study. Arthritis Res. Ther. 2023, 25, 81. [Google Scholar] [CrossRef] [Scilit]
- Aşık, H.K.; Atamer, Y.; Demirel, M.; Şahbaz, T.; Selek, Ş.; Alim, M.; Atamer, A. Nuclear magnetic resonance based metabolomic profiling in fibromyalgia patients. NMR Biomed. 2025, 38, 12. [Google Scholar] [CrossRef] [Scilit]
- Harris, R.E.; Clauw, D.J.; Scott, D.J.; McLean, S.A.; Gracely, R.H.; Zubieta, J.K. Decreased central mu-opioid receptor availability in fibromyalgia. J. Neurosci. 2007, 27, 10000–10006. [Google Scholar] [CrossRef] [Scilit]
- Ayena, J.C.; Bouayed, A.; Ben Arous, M.; Ouakrim, Y.; Loulou, K.; Ameyed, D.; Savard, I.; El Kamel, L.; Mezghani, N. Predicting chronic pain using wearable devices: A scoping review of sensor capabilities, data security, and standards compliance. Front. Digit. Health 2025, 7, 1581285. [Google Scholar] [CrossRef] [Scilit]
- Caro-Alvaro, S.; Garcia-Lopez, E.; Brun-Guajardo, A.; Garcia-Cabot, A.; Mavri, A. Gesture-Based Interactions: Integrating Accelerometer and Gyroscope Sensors in the Use of Mobile Apps. Sensors 2024, 24, 1004. [Google Scholar] [CrossRef] [Scilit]
- Kashikar-Zuck, S.; Flowers, S.R.; Verkamp, E.; Ting, T.V.; Lynch-Jordan, A.M.; Graham, T.B.; Passo, M.; Schikler, K.N.; Hashkes, P.J.; Spalding, S.; et al. Actigraphy-based physical activity monitoring in adolescents with juvenile primary fibromyalgia syndrome. J. Pain 2010, 11, 885–893. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Segura-Jiménez, V.; Álvarez-Gallardo, I.C.; Estévez-López, F.; Soriano-Maldonado, A.; Delgado-Fernández, M.; Ortega, F.B.; Aparicio, V.A.; Carbonell-Baeza, A.; Mota, J.; Silva, P.; et al. Differences in sedentary time and physical activity between female patients with fibromyalgia and healthy controls: The al-Ándalus project. Arthritis Rheumatol. 2015, 67, 3047–3057. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGovney, K.D.; Curtis, A.F.; McCrae, C.S. Associations between objective afternoon and evening physical activity and objective sleep in patients with fibromyalgia and insomnia. J. Sleep Res. 2021, 30, e13220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGovney, K.D.; Curtis, A.F.; McCrae, C.S. Actigraphic Physical Activity, Pain Intensity, and Polysomnographic Sleep in Fibromyalgia. Behav. Sleep Med. 2023, 21, 383–396. [Google Scholar] [CrossRef] [Scilit]
- Birrer, V.; Elgendi, M.; Lambercy, O.; Menon, C. Evaluating reliability in wearable devices for sleep staging. NPJ Digit. Med. 2024, 7, 74. [Google Scholar] [CrossRef] [Scilit]
- Roizenblatt, S.; Moldofsky, H.; Benedito-Silva, A.A.; Tufik, S. Alpha sleep characteristics in fibromyalgia. Arthritis Rheum. 2001, 44, 222–230. [Google Scholar] [CrossRef] [Scilit]
- Lima, D.; Pacheco-Barrios, K.; Slawka, E.; Camargo, L.; Castelo-Branco, L.; Cardenas-Rojas, A.; Neto, M.S.; Fregni, F. The role of symptoms severity, heart rate, and central sensitization for predicting sleep quality in patients with fibromyalgia. Pain Med. 2023, 24, 1153–1160. [Google Scholar] [CrossRef] [Scilit]
- Neikrug, A.B.; Donaldson, G.; Iacob, E.; Williams, S.L.; Hamilton, C.A.; Okifuji, A. Activity rhythms and clinical correlates in fibromyalgia. Pain 2017, 158, 1417–1429. [Google Scholar] [CrossRef] [Scilit]
- Pathak, A.; Kelleher, E.M.; Brennan, I.; Amarnani, R.; Wall, A.; Murphy, R.; Lee, H.; Fordham, B.; Irani, A. Treatments for enhancing sleep quality in fibromyalgia: A systematic review and meta-analysis. Rheumatology 2025, 64, 4495–4516. [Google Scholar] [CrossRef] [Scilit]
- Vincent, A.; Whipple, M.O.; Low, P.A.; Joyner, M.; Hoskin, T.L. Patients with Fibromyalgia Have Significant Autonomic Symptoms But Modest Autonomic Dysfunction. PM&R 2016, 8, 425–435. [Google Scholar]
- Dudarev, V.; Barral, O.; Radaeva, M.; Davis, G.; Enns, J.T. Night time heart rate predicts next-day pain in fibromyalgia and primary back pain. Pain Rep. 2024, 9, e1119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, K.; Lidbury, B.A.; Thomas, N.; Gooley, P.R.; Armstrong, C.W. Machine learning and multi-omics in precision medicine for ME/CFS. J. Transl. Med. 2025, 23, 68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evenson, K.R.; Goto, M.M.; Furberg, R.D. Systematic review of the validity and reliability of consumer-wearable activity trackers. Int. J. Behav. Nutr. Phys. Act. 2015, 12, 159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Zambotti, M.; Cellini, N.; Goldstone, A.; Colrain, I.M.; Baker, F.C. Wearable Sleep Technology in Clinical and Research Settings. Med. Sci. Sports Exerc. 2019, 51, 1538–1557. [Google Scholar] [CrossRef] [Scilit]
- Antikainen, E.; Njoum, H.; Kudelka, J.; Branco, D.; Rehman, R.Z.U.; Macrae, V.; Davies, K.; Hildesheim, H.; Emmert, K.; Reilmann, R.; et al. Assessing fatigue and sleep in chronic diseases using physiological signals from wearables: A pilot study. Front. Physiol. 2022, 13, 968185. [Google Scholar] [CrossRef] [Scilit]
- Jafleh, E.A.; Alnaqbi, F.A.; Almaeeni, H.A.; Faqeeh, S.; Alzaabi, M.A.; Al Zaman, K. The Role of Wearable Devices in Chronic Disease Monitoring and Patient Care: A Comprehensive Review. Cureus 2024, 16, e68921. [Google Scholar] [CrossRef] [Scilit]
- Garcia-Palacios, A.; Herrero, R.; Belmonte, M.A.; Castilla, D.; Guixeres, J.; Molinari, G.; Baños, R.M. Ecological momentary assessment for chronic pain in fibromyalgia using a smartphone: A randomized crossover study. Eur. J. Pain 2014, 18, 862–872. [Google Scholar] [CrossRef] [Scilit]
- Stinson, L.; Liu, Y.; Dallery, J. Ecological Momentary Assessment: A Systematic Review of Validity Research. Perspect. Behav. Sci. 2022, 45, 469–493. [Google Scholar] [CrossRef] [Scilit]
- Okifuji, A.; Donaldson, G.W. Use of ecological momentary assessment to monitor fibromyalgia. Pain Manag. 2011, 1, 195–197. [Google Scholar] [CrossRef] [Scilit]
- Okifuji, A.; Bradshaw, D.H.; Donaldson, G.W.; Turk, D.C. Sequential analyses of daily symptoms in women with fibromyalgia syndrome. J. Pain 2011, 12, 84–93. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.; Dowgwillo, E.A.; Kratz, A.L. Emotional dynamics in fibromyalgia: Pain, fatigue, and stress moderate momentary associations between positive and negative emotions. J. Pain 2023, 24, 1594–1603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bartley, E.J.; Robinson, M.E.; Staud, R. Pain and fatigue variability patterns distinguish subgroups of fibromyalgia patients. J. Pain 2018, 19, 372–381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schneider, S.; Junghaenel, D.U.; Ono, M.; Stone, A.A. Temporal dynamics of pain: An application of regime-switching models to ecological momentary assessments in patients with rheumatic diseases. Pain 2018, 159, 1346–1358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Couto, N.; Monteiro, D.; Cid, L.; Bento, T. Effect of different types of exercise in adult subjects with fibromyalgia: A systematic review and meta-analysis of randomised clinical trials. Sci. Rep. 2022, 12, 10391. [Google Scholar] [CrossRef] [Scilit]
- McMillan, G.; Dixon, D. Self-regulatory processes, motivation to conserve resources and activity levels in people with chronic pain: A series of digital N-of-1 observational studies. Front. Psychol. 2020, 11, 516485. [Google Scholar] [CrossRef] [Scilit]
- Murphy, S.L.; Kratz, A.L. Activity pacing in daily life: A within-day analysis. Pain 2014, 155, 2630–2637. [Google Scholar] [CrossRef] [Scilit]
- Kairys, A.E.; Valentine, T.R.; Whibley, D.; Kratz, A.L. Mind the mood: Momentary depression and anxiety moderate the correspondence between subjective and objective cognitive functioning in fibromyalgia. Arthritis Care Res. 2023, 75, 1967–1975. [Google Scholar] [CrossRef] [Scilit]
- Yoshiuchi, K.; Cook, D.B.; Ohashi, K.; Kumano, H.; Kuboki, T.; Yamamoto, Y.; Natelson, B.H. A real-time assessment of the effect of exercise in chronic fatigue syndrome. Physiol. Behav. 2007, 92, 963–968. [Google Scholar] [CrossRef] [Scilit]
- Moustafa, I.M.; Khowailed, I.A.; Zadeh, S.A.M.; Ozsahin, D.U.; Mustapha, M.T.; Oakley, P.A.; Harrison, D.E. Advanced machine learning applications in fibromyalgia to assess the relationship between 3D spinal alignment with clinical outcomes. Sci. Rep. 2025, 15, 22804. [Google Scholar] [CrossRef] [Scilit]
- Docampo, E.; Collado, A.; Escaramís, G.; Carbonell, J.; Rivera, J.; Vidal, J.; Alegre, J.; Rabionet, R.; Estivill, X. Cluster analysis of clinical data identifies fibromyalgia subgroups. PLoS ONE 2013, 8, e74873. [Google Scholar] [CrossRef] [Scilit]
- Emir, B.; Masters, E.T.; Mardekian, J.; Clair, A.; Kuhn, M.; Silverman, S.L. Identification of a potential fibromyalgia diagnosis using random forest modeling applied to electronic medical records. J. Pain Res. 2015, 8, 277–288. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salgueiro, M.; Basogain, X.; Collado, A.; Torres, X.; Bilbao, J.; Doñate, F.; Aguilera, L.; Azkue, J.J. An artificial neural network approach for predicting functional outcome in fibromyalgia syndrome after multidisciplinary pain program. Pain Med. 2013, 14, 1450–1460. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Braun, A.; Evdokimov, D.; Frank, J.; Pauli, P.; Üçeyler, N.; Sommer, C. Clustering fibromyalgia patients: A combination of psycho-social and somatic factors leads to resilient coping in a subgroup of fibromyalgia patients. PLoS ONE 2020, 15, e0243806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jones, E.A.; Asaad, F.; Patel, N.; Jain, E.; Abd-Elsayed, A. Management of Fibromyalgia: An Update. Biomedicines 2024, 12, 1266. [Google Scholar] [CrossRef] [Scilit]
- Martínez, M.P.; Sánchez, A.I.; Prados, G.; Lami, M.J.; Villar, B.; Miró, E. Fibromyalgia as a Heterogeneous Condition: Subgroups of Patients Based on Physical Symptoms and Cognitive-Affective Variables Related to Pain. Span. J. Psychol. 2021, 24, e33. [Google Scholar] [CrossRef] [Scilit]
- Häuser, W.; Perrot, S.; Clauw, D.J.; Fitzcharles, M.A. Unravelling Fibromyalgia—Steps Toward Individualized Management. J. Pain 2018, 19, 125–134. [Google Scholar] [CrossRef] [Scilit]
- Malik, A.; Brown, Z.; Ryder, A.; Balayan, V.; Jameson, L.; Vu, P.; Al-Jumah, R.; Hasoon, J. Serotonin and Norepinephrine Reuptake Inhibitors (SNRIs) for Treatment of Fibromyalgia: A Comprehensive Clinical Review. Psychopharmacol. Bull. 2025, 55, 24–40. [Google Scholar] [CrossRef] [Scilit]
- Tzellos, T.G.; Toulis, K.A.; Goulis, D.G.; Papazisis, G.; Zampeli, V.A.; Vakfari, A.; Kouvelas, D. Gabapentin and Pregabalin in the Treatment of Fibromyalgia: A Systematic Review and a Meta-Analysis. J. Clin. Pharm. Ther. 2010, 35, 639–656. [Google Scholar] [CrossRef] [Scilit]
- Reed, C.; Birnbaum, H.G.; Ivanova, J.I.; Schiller, M.; Waldman, T.; Mullen, R.E.; Swindle, R. Real-World Role of Tricyclic Antidepressants in the Treatment of Fibromyalgia. Pain Pract. 2012, 12, 533–540. [Google Scholar] [CrossRef] [Scilit]
- Yang, J.; Shin, K.M.; Do, A.; Bierle, D.M.; Abu Dabrh, A.M.; Yin, Z.; Bauer, B.A.; Mohabbat, A.B. The Safety and Efficacy of Low-Dose Naltrexone in Patients with Fibromyalgia: A Systematic Review. J. Pain Res. 2023, 16, 1017–1023. [Google Scholar] [CrossRef] [Scilit]
- Prados, G.; Miró, E.; Martínez, M.P.; Sánchez, A.I.; Lami, M.J.; Cáliz, R. Combined Cognitive-Behavioral Therapy for Fibromyalgia: Effects on Polysomnographic Parameters and Perceived Sleep Quality. Int. J. Clin. Health Psychol. 2020, 20, 232–242. [Google Scholar] [CrossRef] [PubMed]
- Schmidt, S.; Grossman, P.; Schwarzer, B.; Jena, S.; Naumann, J.; Walach, H. Treating Fibromyalgia with Mindfulness-Based Stress Reduction: Results from a 3-Armed Randomized Controlled Trial. Pain 2011, 152, 361–369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Richards, S.C.; Scott, D.L. Prescribed Exercise in People with Fibromyalgia: Parallel Group Randomised Controlled Trial. BMJ 2002, 325, 185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loftus, N.; Dobbin, N.; Crampton, J.S. The Effects of a Group Exercise and Education Programme on Symptoms and Physical Fitness in Patients with Fibromyalgia: A Prospective Observational Cohort Study. Disabil. Rehabil. 2022, 44, 3860–3867. [Google Scholar] [CrossRef] [Scilit]
- Wu, Y.L.; Fang, S.C.; Chen, S.C.; Tai, C.J.; Tsai, P.S. Effects of Neurofeedback on Fibromyalgia: A Randomized Controlled Trial. Pain Manag. Nurs. 2021, 22, 755–763. [Google Scholar] [CrossRef] [Scilit]
- Carneiro, B.D.; Torres, S.; Costa-Pereira, J.T.; Pozza, D.H.; Tavares, I. Descending Pain Modulation in Fibromyalgia: A Short Review of Mechanisms and Biomarkers. Diagnostics 2025, 15, 2702. [Google Scholar] [CrossRef] [Scilit]
- Gerdle, B.; Ghafouri, B.; Lund, E.; Bengtsson, A.; Lundberg, P.; Ettinger-Veenstra, H.v.; Leinhard, O.D.; Forsgren, M.F. Evidence of Mitochondrial Dysfunction in Fibromyalgia: Deviating Muscle Energy Metabolism Detected Using Microdialysis and Magnetic Resonance. J. Clin. Med. 2020, 9, 3527. [Google Scholar] [CrossRef] [Scilit]
- Ablin, J.N.; Buskila, D. Fibromyalgia Syndrome—Novel Therapeutic Targets. Maturitas 2013, 75, 335–340. [Google Scholar] [CrossRef] [Scilit]
- Sun, P.; Fang, L.; Zhang, J.; Liu, Y.; Wang, G.; Qi, R. Repetitive Transcranial Magnetic Stimulation for Patients with Fibromyalgia: A Systematic Review with Meta-Analysis. Pain Med. 2022, 23, 499–514. [Google Scholar] [CrossRef] [Scilit]
- Cheng, Y.C.; Hsiao, C.Y.; Su, M.I.; Chiu, C.C.; Huang, Y.C.; Huang, W.L. Treating Fibromyalgia with Electrical Neuromodulation: A Systematic Review and Meta-Analysis. Clin. Neurophysiol. 2023, 148, 17–28. [Google Scholar] [CrossRef] [Scilit]
- Zhao, F.; Zhao, J.; Li, Y.; Song, C.; Cheng, Y.; Li, Y.; Wu, S.; He, B.; Jiao, J.; Chang, C. Identification of diagnostic biomarkers for fibromyalgia using gene expression analysis and machine learning. Front. Genet. 2025, 16, 1535541. [Google Scholar] [CrossRef] [Scilit]
- Freidlin, B.; Korn, E.L. Biomarker Enrichment Strategies: Matching Trial Design to Biomarker Credentials. Nat. Rev. Clin. Oncol. 2014, 11, 81–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- El Miedany, Y.; El Gaafary, M.; Youssef, S.; Ahmed, I. Towards Tailored Patient’s Management Approach: Integrating the Modified 2010 ACR Criteria for Fibromyalgia in Multidimensional Patient Reported Outcome Measures Questionnaire. Arthritis 2016, 2016, 5371682. [Google Scholar] [CrossRef] [Scilit]
- Prikhodkina, M.; Melnikov, S. Factors That Influence Medication Adherence in Women with Fibromyalgia: A Path Analysis. J. Clin. Nurs. 2024, 33, 3943–3953. [Google Scholar] [CrossRef] [Scilit]
- Vázquez-González, G.; Allande-Cussó, R.; Gómez-Salgado, J.; Yildirim, M.; Fagundo-Rivera, J.; Climent-Rodríguez, J.A.; Navarro-Abal, Y. Prejudices, Attitudes, and Stereotypes of Healthcare Professionals Towards Fibromyalgia: A Systematic Review. Aten. Primaria 2025, 57, 103251. [Google Scholar] [CrossRef] [Scilit]
- Ahmed, L.; Constantinidou, A.; Chatzittofis, A. Patients’ Perspectives Related to Ethical Issues and Risks in Precision Medicine: A Systematic Review. Front. Med. 2023, 10, 1215663. [Google Scholar] [CrossRef] [Scilit]
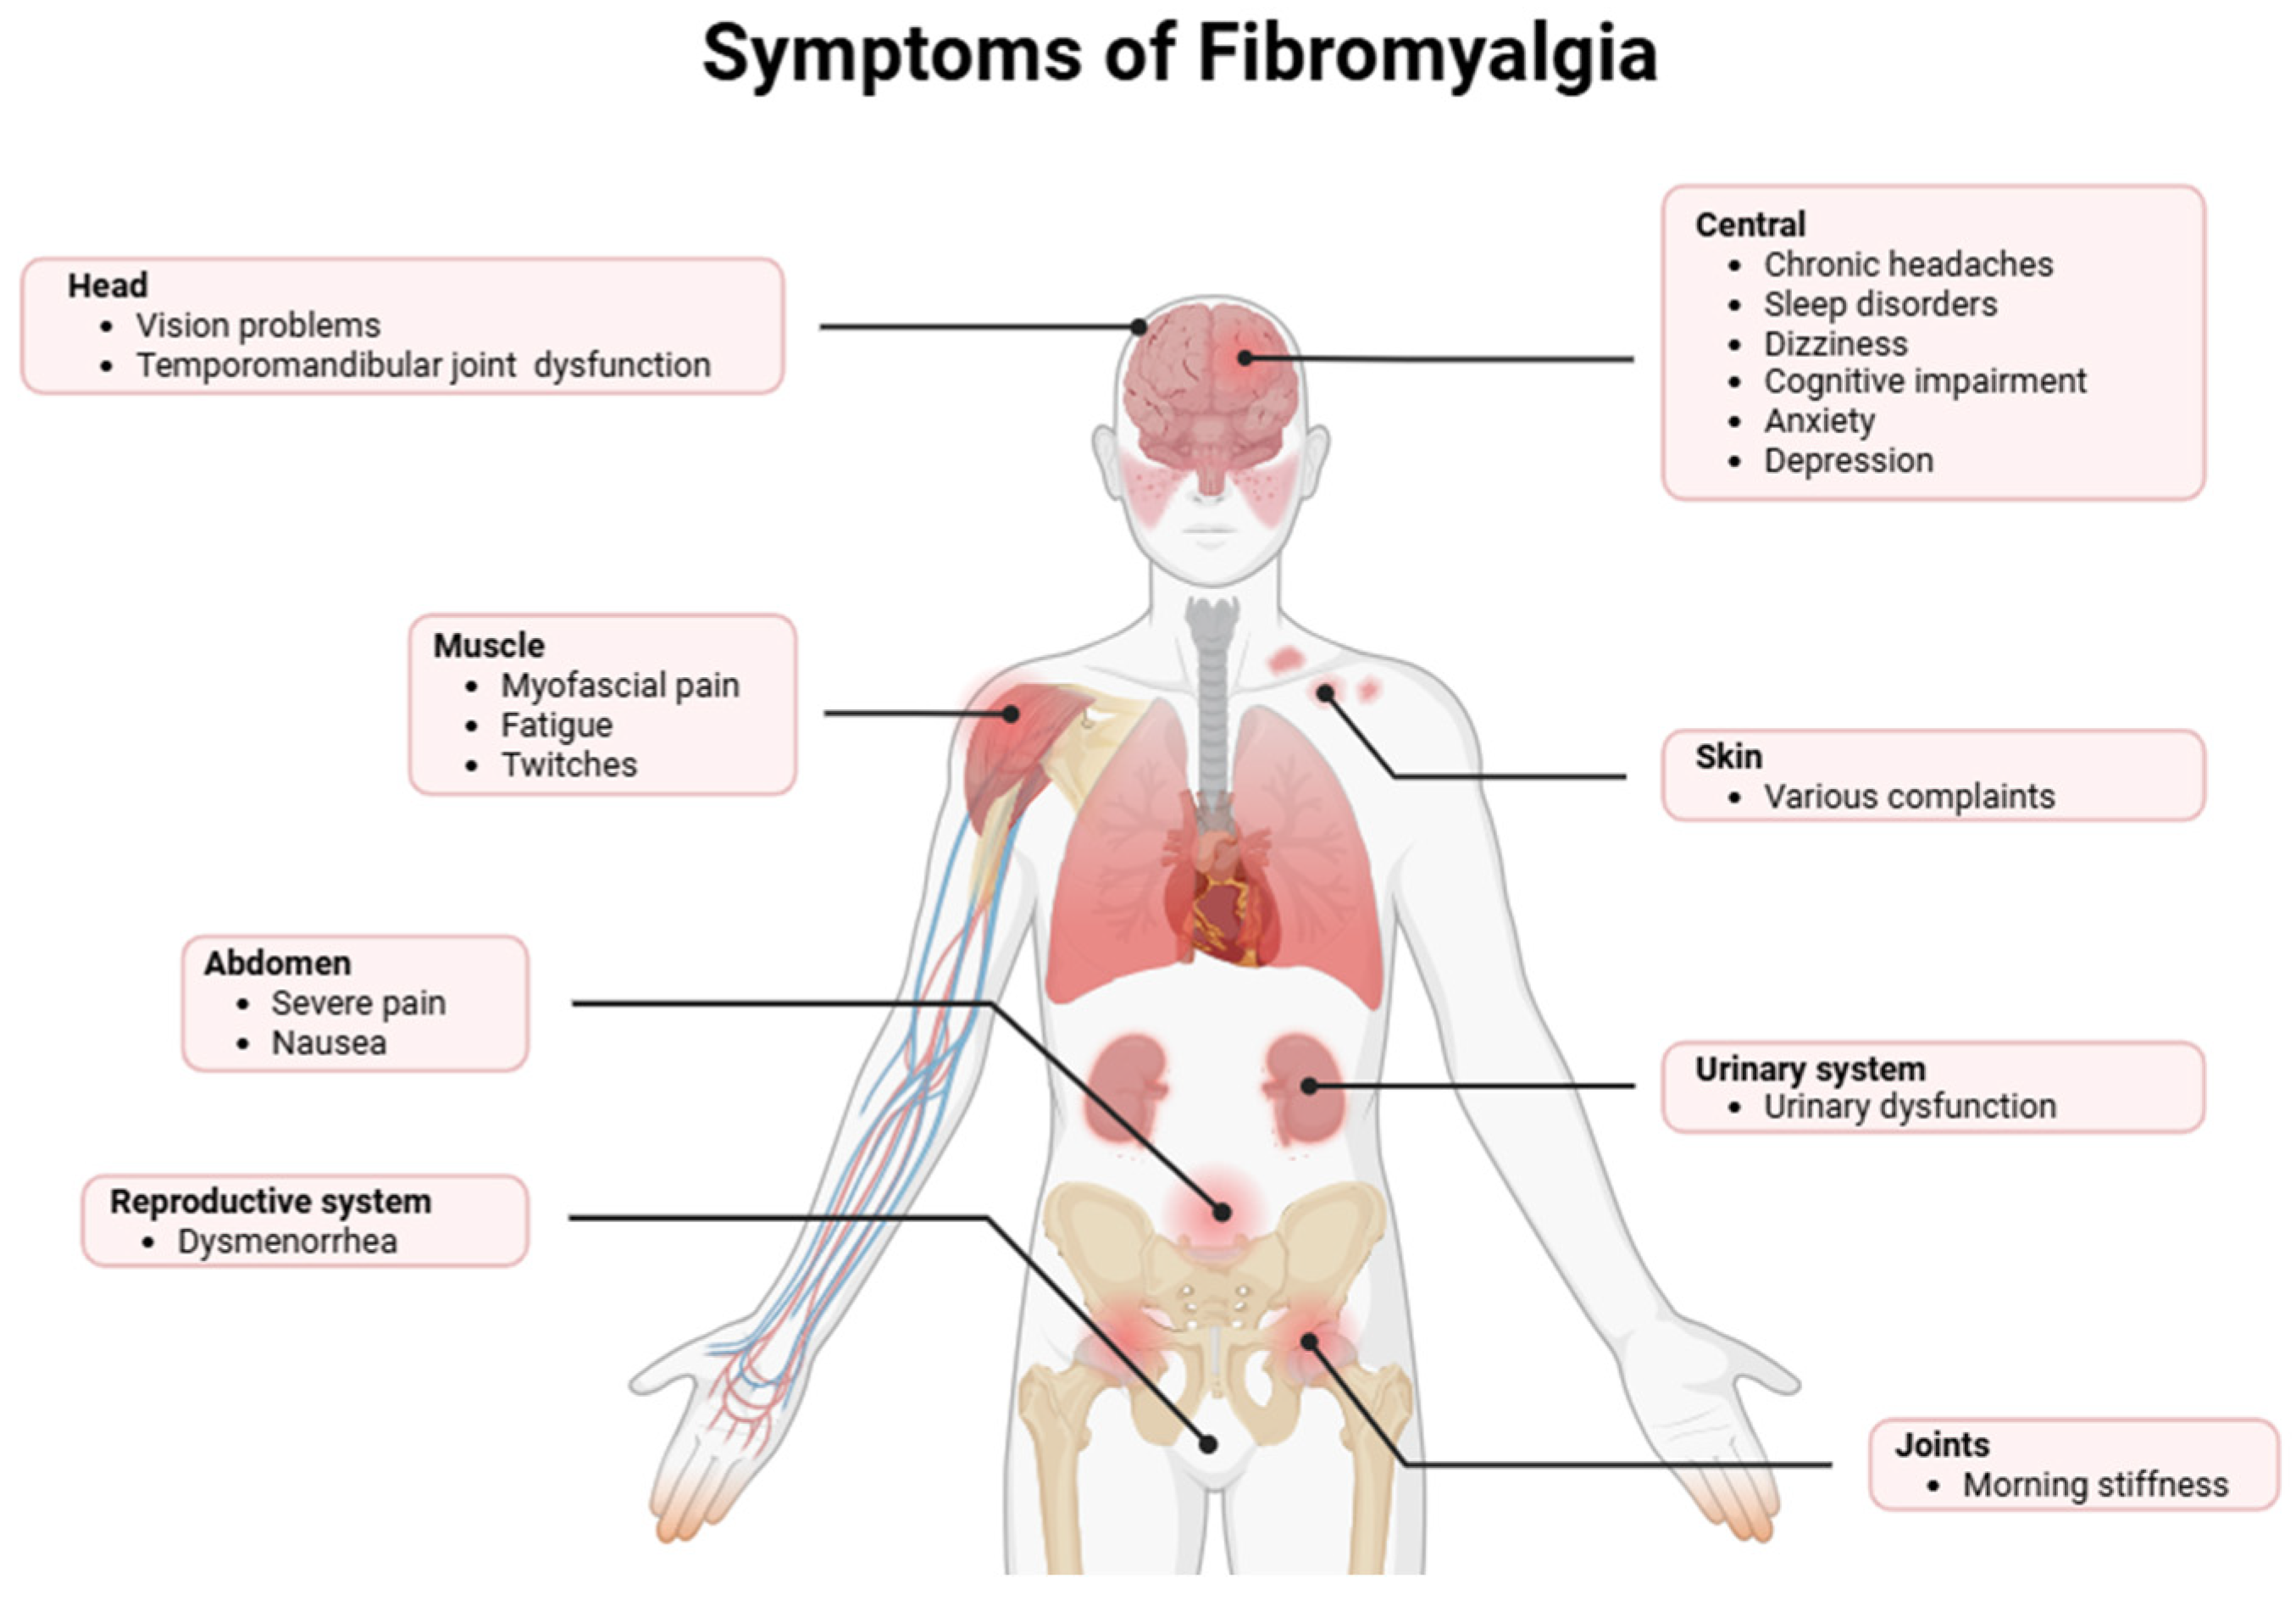

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.