


Abstract
Background: Emergency departments (ED) are vital within the health system, often representing the first hospital contact for patients who are undifferentiated and may be critically ill. Although advancements in digital technology and increasing use of electronic medical records in health systems have led to the dramatic growth of large data sets, the presence of ED clinical registries to measure quality of care in the literature is currently unknown. Objectives: Our scoping review aims to investigate the extent of emergency department clinical registries reported in peer-reviewed literature. Methods: We conducted a scoping review of ED registries in accordance with the PRISMA-ScR checklist. Searches were undertaken in PUBMED, EMBASE, and SCOPUS. Studies were included if they described a clinical registry with a focus on the ED. Results: We identified 60 manuscripts with 27 identified as primary registries (6 had a general scope, 21 were condition or population specific). The remaining 33 papers were investigational reports sourced from the identified primary registries. Funding sources were identified for some registries: three by research grants, two by medical colleges, five by government organizations or initiatives, two by pharmaceutical companies, and three by research institutes. No funding information was provided in 12 studies. The reported registry periods ranged from 31 days to 4018 days (median 365 days, IQR 181–1309 days). A grey literature search revealed that six registries were ongoing. Conclusions: Internationally, there appears to be a wide degree of heterogeneity with primary ED registry publications and secondary publications. Having a standardized approach to ED registries is needed. Integrating ED registries with a learning health system model will enable clinicians to serve their community proactively and with a focus on quality, rather than the current safety-focused approach.
1. Introduction
Emergency departments (EDs) play a vital role within the health system, often representing the first point of hospital contact for patients who are undifferentiated and may be critically ill [1]. The ED manages a high volume of patients who range in acuity from the critically ill through to the worried well. This places a significant burden on ensuring timely diagnosis and management to avoid potentially avoidable adverse outcomes from care [2]. The ED is therefore a patient care environment that is highly vulnerable to the provision of low-quality care and breaches in patient safety [3]. The exponential growth of ED overcrowding creates further challenges to delivering standardized, high-quality care [4].
A variety of solutions have been developed to try and counter these challenges, including guidelines, policies, and pathways. Despite these best intentions, EDs remain significantly unsafe [5]. In recent years, advancements in digital technology and increasing use of electronic medical records in health systems have led to dramatic growth in large clinical data sets. Harnessing these data to improve health care has taken on many forms and defined in different ways to include databases, audits, and registries. These registries, along with databases and audits, provide a comprehensive framework for tracking patient outcomes, identifying best practices, and facilitating evidence-based decision-making. By harnessing this wealth of information, healthcare providers can pinpoint areas for improvement, tailor treatments to individual patient needs, and ultimately deliver more effective and personalized care. Patient registries can be defined as organized systems that use observational study methods to collect uniform data (clinical and other) to evaluate specified outcomes for a population defined by a particular disease, condition, or exposure, and that serve a predetermined scientific, clinical, or policy purpose(s) [6]. Audits on the other hand can be seen as one-off collections of data.
Clinical quality registries (CQRs) have emerged as a necessary approach to systematically collect, analyze, and report information about the care and outcomes being delivered by health service organizations, and serve as a fundamental driver for ongoing improvements in the delivery of safe and high-quality care [7]. Mature CQRs such as the Australian and New Zealand Intensive Care Society Centre for Outcomes and Resources Evaluation (ANZICS CORE) have the capability to also shape health policy, integrate data through linkage projects, and inform clinical practice in real time whilst also providing infrastructure for measuring the translation of evidence into practice [8]. For emerging areas of health care, CQRs have been shown to be a catalyst to create clinical evidence for the development of best practice guidelines such as the Burns Registry of Australia and New Zealand [9]. Since care for many diseases and illnesses as well as the utilization of specific healthcare resources, such as trauma teams, occur within the ED, the data reflecting the ED phase of care are being collected for these related CQRs. However, given the breadth and varied governance of these CQRs, ED staff often have little input into their methodology, maintenance, analysis, and interpretation [2].
Clinical quality registries can be categorized across three broad areas: (1) procedures, devices, or drugs, (2) disease or illness, or (3) specific healthcare resource (Table 1) [10]. Although there is no international repository for CQRs, country-level repositories do exist. The National Institutes of Health have a list of 81 registries, and the Australian Commission on Safety and Quality in Health Care have developed the Australian Register of Clinical Registries, which currently lists 125 CQRs [11,12].
Table 1.
Categories and examples of clinical quality registries.
Each CQR category presents their own challenges for creating a registry. Potential barriers to constructing an informed ED registry include determining key quality outcome measures. On a more technical level, the volume and heterogeneity of patients and potential data points for collection, rapid turnover, heterogeneous data handling, storage and retrieval, rigorous national and state data privacy laws, and institutional and jurisdictional requirements for data sharing agreements pose significant challenges to creating an ED registry [18]. Finally, the financial outlay for the significant infrastructure required to support an ED CQR can be a barrier.
To our knowledge, a review of ED-focused CQRs has not been published. Our scoping review aims to investigate the breadth of emergency department (ED) clinical registries documented in peer-reviewed literature.
2. Methods
This scoping review was guided by the Joanna Briggs Institute methodology for scoping reviews and in compliance with the Preferred Reporting Items for Systematic reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) recommendations (Supplementary Table S1) [19,20]. The search protocol was developed by VT, GB, and SP and objectives, search methods, and registry inclusion criteria were prespecified before the commencement of the study. This study did not require approval by an institutional ethical review board as no individual patient data were included and data regarding registries were publicly available. Preregistration of the study protocol was published in Inplasy (INPLASY202440119—https://inplasy.com/inplasy-2024-4-0119 accessed on 29 April 2024) prior to commencement.
2.1. Search Strategy
The search strategy (Appendix A) was developed in accordance with the Peer Review of Electronic Search Strategies (PRESS) criteria [21]. The following electronic databases were searched: National Library of Medicine via PubMed, Embase, and Web of Science and were chosen as they collectively provide comprehensive coverage of biomedical literature, ensuring a thorough and diverse range of relevant studies [22]. The search period included date of database inception to April 2024.
The results of the database searches were screened using the web-based reviewing platform CovidenceTM (Veritas Health Innovation, Melbourne, Australia). Duplicate studies were removed. Title and abstract screening were performed independently by authors VT and GB where suitability for inclusion was assessed against the eligibility criteria. Following title and abstract screening, identified publications were retrieved and imported to CovidenceTM for full text review. Full-text screening of all included publications was performed by authors VT and GB independently. Any disagreements between reviewers during screening of title and abstract or full text were resolved through discussion with a third review author (SP) on the study team.
For publications where it became apparent that they were referencing a registry, a search for the registry occurred using the name of the registry in the PUBMED database to identify the primary publication for that registry.
2.2. Eligibility Criteria
2.2.1. Inclusion Criteria
Full-text articles published in English describing ED registries were included. We defined an ED registry as a systematic data collection program (using a database, databank, or register) for monitoring standardized indicators of care quality (including safety) where ED care was the focus. Our inclusion and exclusion criteria only considered registries where the ED led the registry setup and maintenance. By having the ED as the lead department, it ensures that the most appropriate metrics are being measured to answer questions fundamental to the quality of care in the ED. Furthermore, ED staff will have the greatest understanding of the data, its interpretation, and, most importantly, its limitations [18]. Publications were included from protocol publication through to secondary analysis of registry data. Single-center, multicenter, regional, statewide, national, and multinational registries were also included.
2.2.2. Exclusion Criteria
Publications were excluded if they were developed for epidemiological disease monitoring without collection of clinical care indicators. Publications were also excluded if they were purely for administrative, system monitoring, or financial purposes. Publications where the primary locus of care was not in the ED were excluded. Publications that were case reports, case series, narrative reviews, editorials, short communications, case studies, or conference abstracts were also excluded. Non-human studies were also excluded.
2.3. Data Extraction and Analysis
Data were extracted from included papers by authors VT and SP. Uncertainties or discrepancies were resolved through discussion with a third review author (GB). The data extraction template included funding source, trial number, type of registry, target demographic, population of interest, start and end dates for the registry, inclusion and exclusion criteria, data sources, collection tools, data entry procedures, number of participants included in the registry, availability of a data dictionary and data sharing arrangements, country of origin, number of participating Eds, and ethical approvals.
Registries identified were categorized based on their scope as well as on the sequence in which they were published. For scope, ED registries were described as general if the inclusion criteria included all ED presentations and conditions, or condition or population specific if the data captured were restricted. For studies that identified an ED registry within the search strategy more than once, the oldest paper was considered the primary registry publication and subsequent papers as secondary publications.
Aims, objectives, results, and conclusions were also extracted from publications to understand how registry data are being used. Included studies were not appraised for methodological quality or risk of bias as this is not customary for scoping reviews.
Data analysis included developing summary statistics and frequency counts. SP developed summary tables.
3. Results
3.1. Search Results
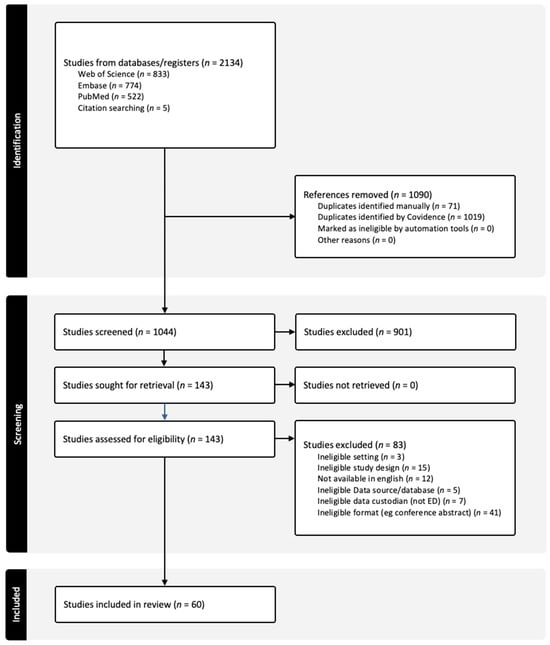
The initial literature search identified 2134 publications (Figure 1). After removal of 1090 duplicates, 901 studies were not eligible based on title and abstract screening by two independent reviewers (VT and GB). Of the 143 full-text publications acquired and screened independently by VT and GB, a further 83 publications were excluded due to a variety of reasons described in the PRISMA flow diagram (Figure 1), such as ineligible format (conference abstract) or ineligible data custodian (not an ED). As a result, 60 studies were eligible for review (Table 2) [23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81,82,83]. Notably, there were six general registries and six airway-specific registries with few secondary publications from general registries.
Figure 1.
PRISMA diagram summarizing the search strategy used to identify emergency department clinical quality registries meeting inclusion criteria.
Table 2.
Count of ED clinical quality registries by type and scope of registry.
3.2. Characteristics of Primary ED Registry Publications
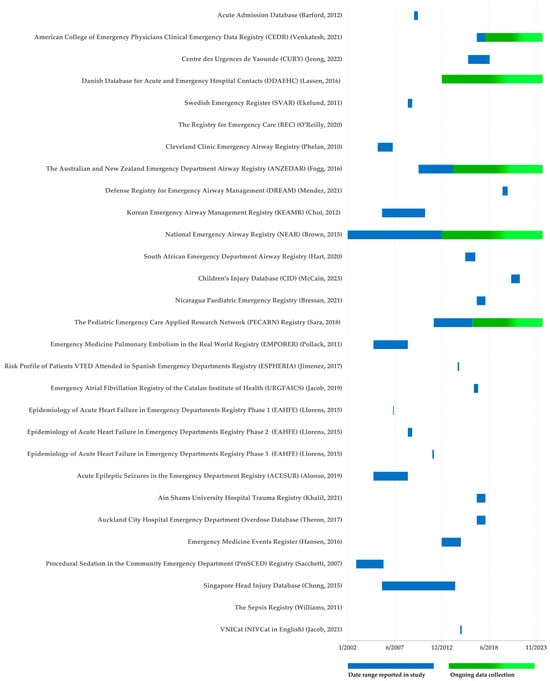
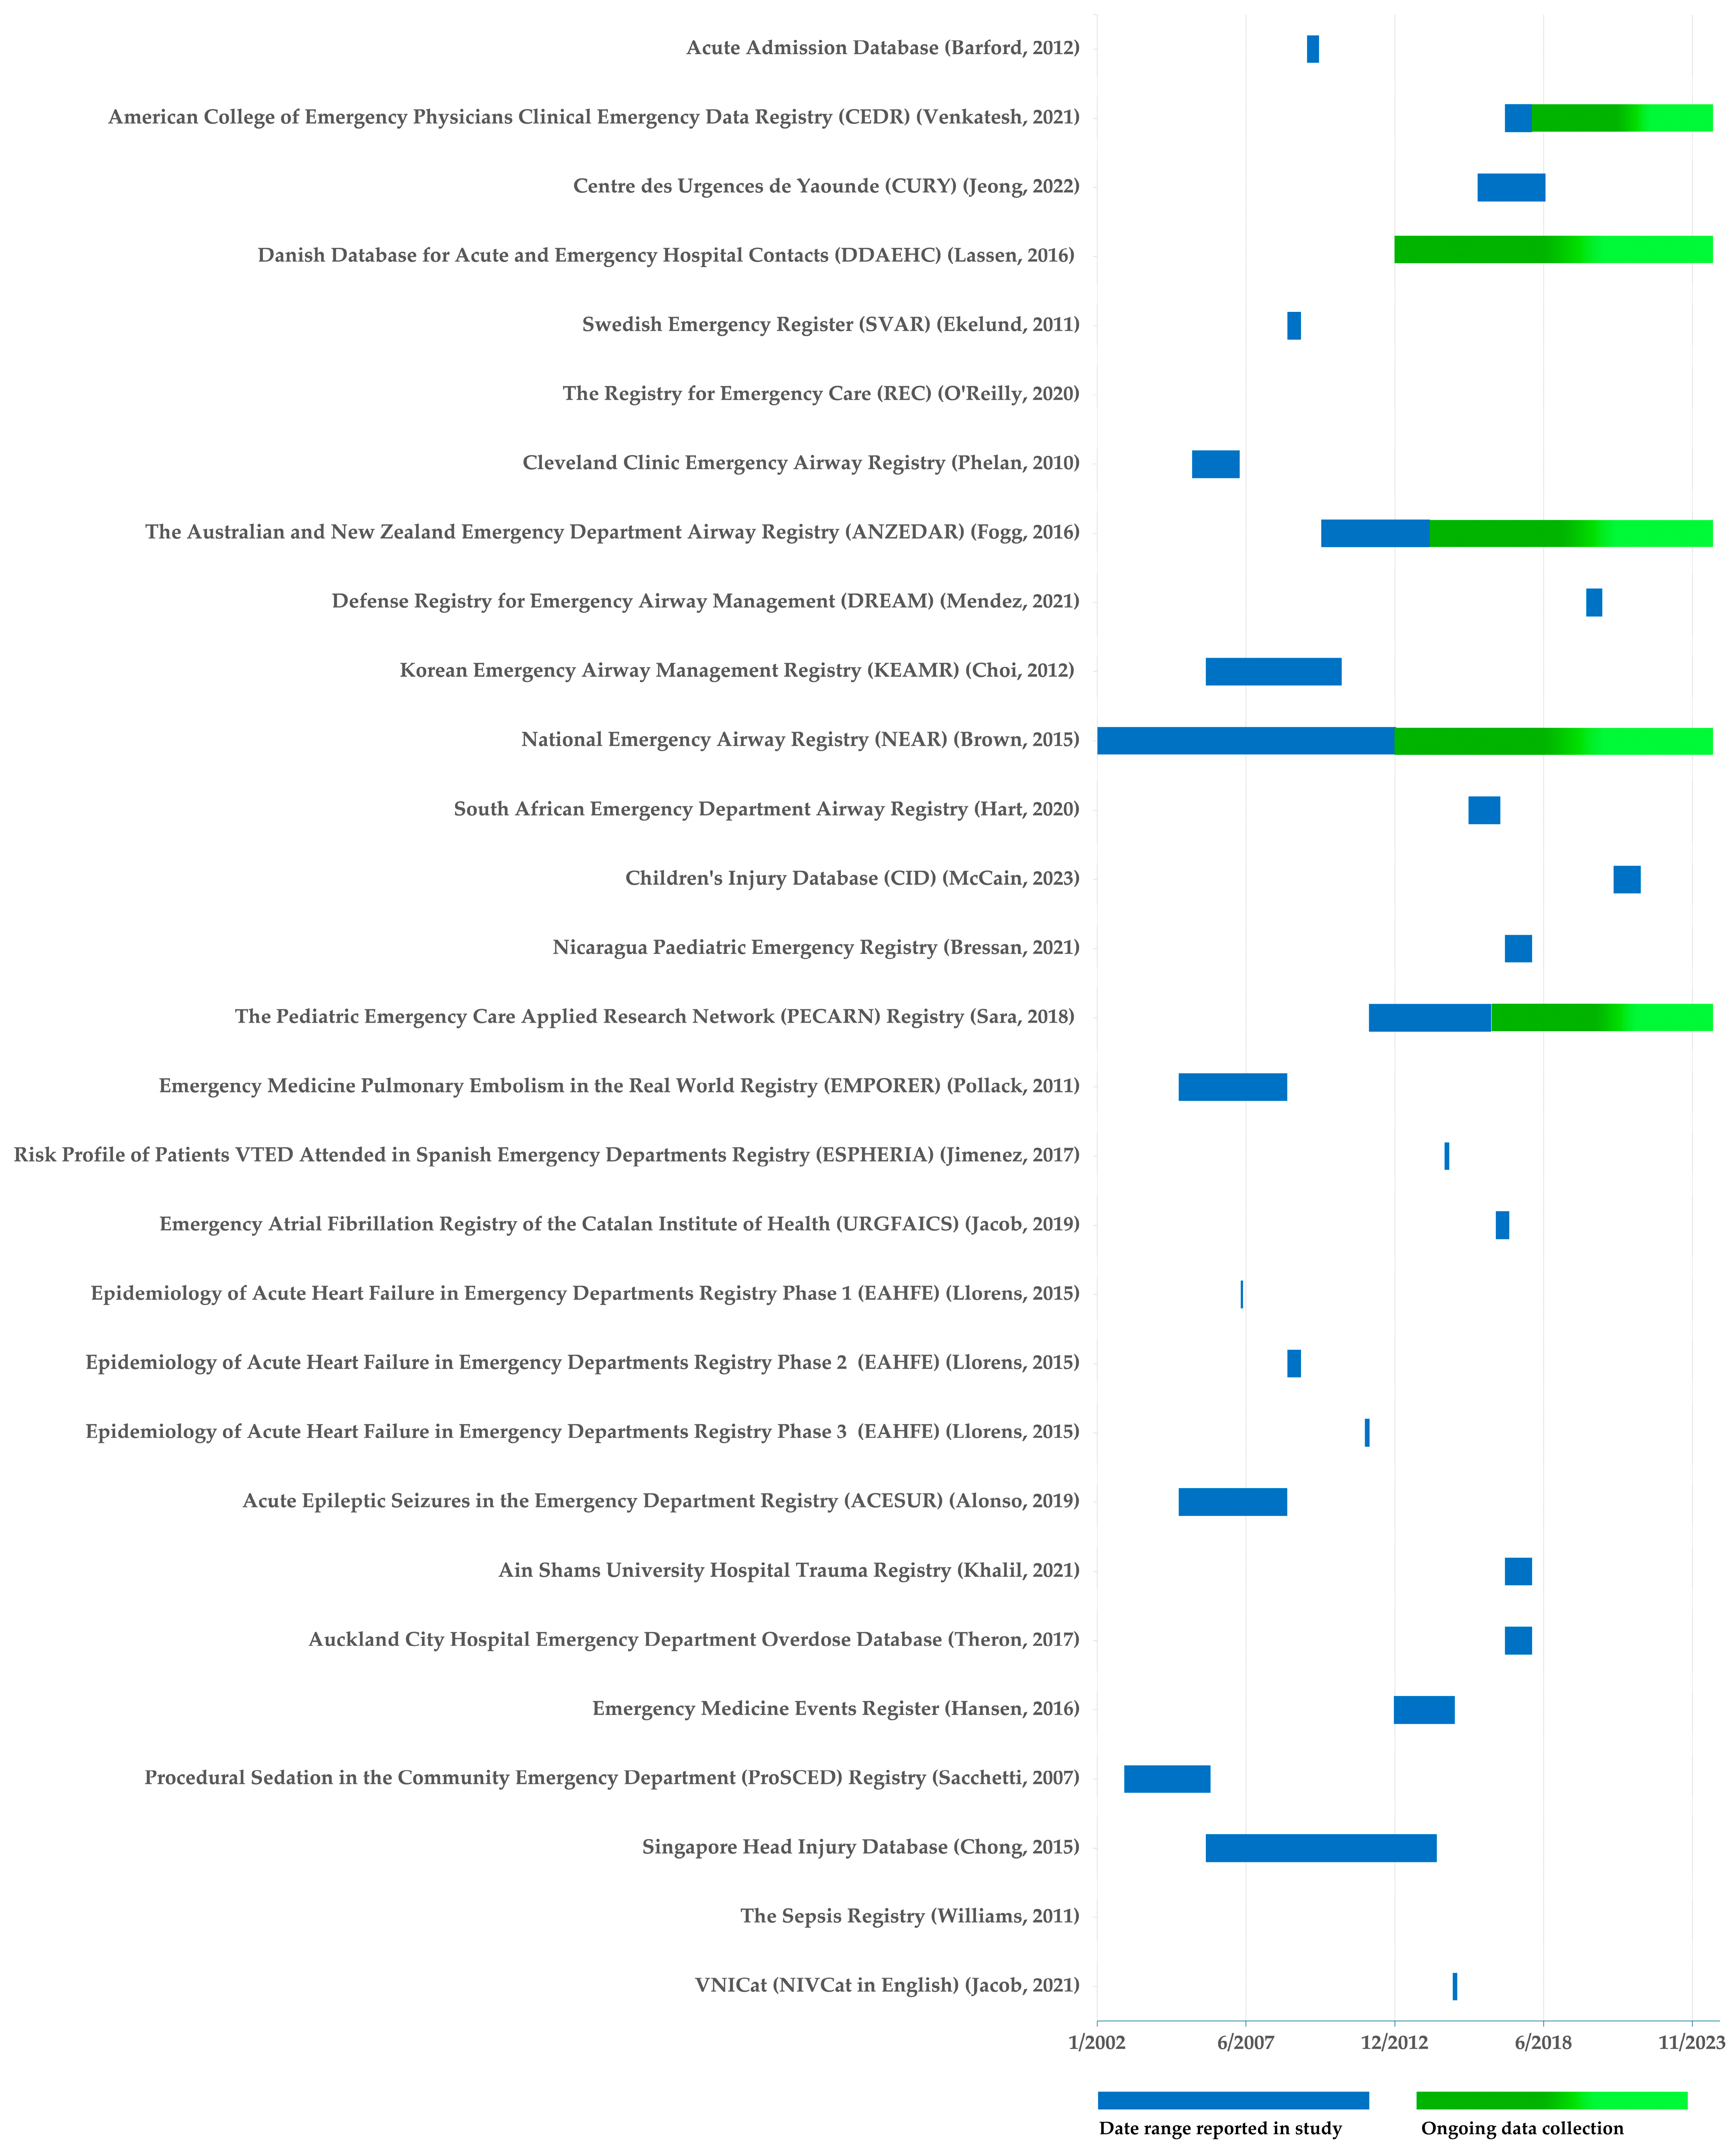
Our scoping review yielded 27 registries that fit the inclusion criteria for a primary ED registry publication (Table 2). Six of these registries were general ED registries. Three registries were specific to the same population, namely pediatrics. The remaining 18 registries were specific to a condition. Airways was the most common condition with six registries, followed by two registries that covered different aspects of venous thromboembolism. The remaining ED registries addressed independent conditions. The number of EDs involved in each registry varied from 1 to 889 (median 5.5, IQR 1–14). Country representation included a total of 13 countries with USA the most frequently contributing with eight registries (two general, six specific) followed by Australia with five (one general, four specific), Denmark two (two general, zero specific), Spain four (zero general, four specific), and New Zealand two (zero general, two specific). The reported registry periods ranged from 31 days to 4018 days (median 365 days, IQR 181–1309 days). Following a grey literature search of the 27 primary ED registry publications, 6 were found to be ongoing; 3 general, 2 airway-specific, and 1 pediatric-specific. Distribution of these registries over time is shown in Figure 2.
Figure 2.
Timeframes for primary ED registry publications [23,24,27,30,33,34,35,39,43,44,45,47,48,49,51,53,54,55,56,57,58,60,62,63,65,71,74,76].
3.3. Funding for Primary ED Registry Publications
For registries where funding was acknowledged, three were funded by research grants, two by medical colleges, five by government organizations or initiatives, two by pharmaceutical companies, and three by research institutes. For registries identified as ongoing (Figure 2), sources of funding were identified as medical college for one registry, government organization or initiative for three registries, research grants for one registry, and no funding acknowledged for one registry. Twelve of the twenty-seven primary ED registry publications did not acknowledge any funding for the registries described. Funding amounts were not described for any of the studies.
3.4. Aims, Results, and Conclusion in Primary ED Registry Publications with a General Scope
Aims, results, and conclusions for primary ED registry publications with a general scope provided insight into the breadth of each manuscript (Table 3). Three publications focused on registry methodology, feasibility and evaluation, while two described its use for performance measurements and one described its use for measuring the quality of clinical care.
Table 3.
Aims, results, and conclusion of primary ED registry publications.
For publications that focused on registry methodology, feasibility, and evaluation, 2 concluded that creating a registry and evaluating a pilot project was feasible, with the other describing methodology without acknowledging feasibility. One paper also described a desire to expand the dataset to include non-ED metrics, another described the potential for use in quality improvement, and the last described expansion to additional EDs.
Lassen et al. [48] was the only general primary ED registry publication that described the evaluation of quality of clinical care. Notably, this registry included specific outcomes and process health care quality indicators. Performance measures in the ED are often represented by time-based targets including length of time in the ED and time awaiting medical review. Two general ED registries described the use of a registry to inform these performance measures, although one paper was simply the protocol.
3.5. Aims, Results and Conclusion in Primary ED Registry Publications Specific for a Condition or Population
Aims, results, and conclusions for primary ED registry publications specific for a condition or population provided insight into the scope of each manuscript (Supplementary Table S2). Unlike general scope primary ED registry publications, condition-specific primary ED registry publications focused on clinical quality including evaluating or benchmarking against standards. The only population-specific registries were for pediatrics, and these were similar to general scope primary ED registry publications focusing on registry methodology, feasibility, and evaluation.
3.6. Aims, Results and Conclusion in Secondary Publications
Of the 27 primary ED registry publications, 16 did not have a secondary study (Table 3). Of those that did have secondary publications, the median number of studies was 1 (IQR 1–2). Two general ED registries each had 1 secondary publication while 24 secondary publications were identified for all airway-specific registries with the NEAR registry accompanied by 19 associated studies (Table 4).
Table 4.
General characteristics of ED clinical quality registries.
Aims, results, and conclusions for secondary publications were similar to their primary ED registry publications (Supplementary Table S3). Secondary publications with a focus on specific conditions reported on clinical quality through a variety of means, including benchmarking and describing trends in practice. Secondary publications with a general scope reported on performance indicators in the form of time-based performance.
4. Discussion
Emergency departments are often tasked with managing a high proportion of undifferentiated patients who range from the critically ill through to the worried well [2]. This combination of undifferentiated and unwell patients places a significant burden on ensuring timely diagnosis and management to avoid significant adverse outcomes from care [2]. Clinical registries are focused on the quality of health care within specific clinical domains by systematically analyzing health-related data for an eligible population and serves as an efficient approach to the assessment of quality care in the ED setting [7]. This scoping review sought to understand the current use of ED registries.
4.1. Emergency Department Registries Reported in the Literature
Our review identified 27 primary ED registry publications, representing a diverse range of focuses and geographical representations. Notably, most registries were condition-specific, with airway being by far the most common condition studied (33.3% of all condition-specific primary ED registry publications). This may represent the fact that airway management in the ED setting is of critical importance [84]. It may also be that there are more reproducible clinical quality measures within the process of airway management in this setting [84]. The reality is likely to be multifactorial but suggests that airway registries may be more feasible at a local level and therefore individual EDs or networks of EDs could consider establishing or contributing to an ED airway registry to pilot the creation of a registry in the ED. This process would assist in understanding the technical requirements as well as local ethical, governance, and data sharing requirements prior to embarking on a larger registry.
Whereas condition- or population-specific ED registries offer an easier approach to understanding the infrastructure needs for local registry set up and maintenance, general ED registries serve a broader purpose given the general nature of emergency medicine as a specialty and the need to interrogate many aspects of this heterogenous patient population. The difference between condition- or population-specific registries and general registries is therefore vastly different and requires a significantly higher investment both financially and administratively. All the general ED registries included in our search strategy utilized a largely administrative data set. This seems to be the most practical method for developing general ED registries, though it is limited primarily to performance data, particularly time-based targets. A natural evolution should involve the inclusion of clinical data to shift the analysis to clinical care and patient-centered outcomes. How clinical data is linked to administrative data and what clinical data should be prioritized for capture are all considerations that will require further research and consensus with the involvement of consumers and policymakers alike [18].
4.2. Emergency Department Registry Scope
The analysis of primary ED registry publications specific to conditions or populations revealed distinct trends and focuses compared to general scope primary ED registry publications. Condition-specific registries predominantly emphasized clinical quality, often through evaluation and benchmarking against established standards. This focus on clinical quality underscores the importance of these registries in enhancing patient care and outcomes by providing a framework for continuous improvement and adherence to best practices.
In contrast, the only population-specific registries identified were those targeting pediatric populations. These registries shared similarities with general scope primary ED registry publications, particularly in their emphasis on registry methodology, feasibility, and evaluation. This alignment suggests that while the target population may differ, the foundational principles guiding the development and implementation of these registries remain consistent.
Our scoping review describes a largely heterogenous set of ED registries. As a result of this, quality indicators were not well described. To enhance the selection of quality indicators, it would be advantageous to adopt a stakeholder-driven approach. This approach should prioritize the values of patients and communities, as well as the actionable improvement priorities identified by healthcare providers. Additionally, there should be a greater emphasis on measuring distinct and discernible processes of care [85].
4.3. Temporal Scope of Emergency Department Registries
Most registries were time-limited, with a median duration of one year (0.05–3.59 years). A grey search of all primary ED registry publications recognized six of these registries as ongoing, three of which are general ED registries. This time limitation may exist for a variety of reasons. It may reflect the challenges associated with sustaining long-term registry efforts, including funding, data collection, and maintenance. A more plausible explanation is that researchers use the term registry interchangeably with traditional data collection tools for audit or research and databases that do not meet the criteria of a registry [6].
4.4. Funding Source for Emergency Department Registries
Health economic studies have demonstrated that relatively small injections of funding to supplement existing efforts at creating and maintaining a clinical registry is likely to be highly cost effective [86,87]. The funding sources described for the registries identified were varied, ranging from hospital-based funding to government organizations and pharmaceutical companies. Nearly half of the registries did not acknowledge any funding, which raises questions about sustainability and potential biases in the data collection processes. For the registries that did report funding, government organizations and research institutes were the most common sources. Of all registries that were ongoing, only three of the five had reported funding, which suggests the role of funding may only be one part of a successful registry.
None of the studies reported the amount of funding provided for either registry-related costs or study-related costs. This would have been useful to provide an indication for those wanting to initiate a registry to better understand the financial requirements and align funder expectations. Future studies should aim to provide more transparency in funding to better understand the resources required for developing, maintaining, and interrogating registry data.
4.5. ED Registries as a Catalyst for Further Publications
The examination of secondary publications reveals the impact and scope of these registries. Of the 27 primary ED registry publications analyzed, 16 did not have any secondary publications, highlighting a potential area for future research and exploration. Some non-ED registries such as the Australian Trauma Registry have been successful with more abundant reporting with over 14 secondary publications since the registry started in 2012 [88]. One hypothesis includes the lack of ongoing funding to support such endeavors. For those registries with secondary publications, the median number of studies was relatively low, with a median of 1 (IQR 1–2). This finding suggests that while some registries are actively contributing to the research landscape, there is significant room for expansion and the barriers for these should be explored.
Interestingly, the NEAR registry, an airway-specific registry, stood out with 19 secondary publications, indicating a robust research output and a strong focus on airway management within the ED context. This contrasts with the general ED registries, which had fewer secondary publications. The secondary publications for condition-specific registries primarily reported on clinical quality through various means, including benchmarking and trend analysis.
4.6. ED Registries as a Catalyst for Quality—A Piece of the Learning Health System Puzzle?
Registries themselves serve as a rich source of data and on their own serve no other purpose. It is up to policy makers, ED administrators, and clinicians to utilize these data to deliver these quality initiatives. Although quality and safety are often used in the same phrase, the current driver for enhancing care prioritizes the delivery of safe (rather than quality) care. In the context of resource-poor services, the result of this focus is a system that is reactive without the opportunity or resources to focus on quality. Learning health systems (LHSs) have emerged as a popular concept to bring focus back on quality through a standardized framework [89]. The Institute of Medicine coined the term Learning Health System (LHS) in 2007, describing it as a health system where “science, informatics, incentives, and culture are aligned for continuous improvement and innovation, with best practices seamlessly embedded in the care process, patients and families active participants in all elements, and new knowledge captured as an integral by-product of the care experience” [89]. Although there is debate around a specific definition for an LHS, a review of bibliometric trends for LHSs found a large degree of convergence describing LHSs as ‘achieving healthcare quality improvement by using big data and embedding data analysis and intelligent decision-making into routine care delivery processes’ [90]. A fundamental requirement for this system to work, and indeed any quality improvement strategy, relies on the availability of data relevant to the quality being evaluated. The appeal of registries in the ED setting is that quality can be truly assessed on a broad level compared with current ad hoc strategies that realistically result in no evaluation and therefore limited understanding of the true quality of care being delivered.
5. Limitations
There are several limitations to this review. The search strategy used terms in English. Limiting our scoping review to only English language papers can introduce language bias and geographic bias, potentially excluding relevant studies published in other languages and thereby affecting the comprehensiveness and generalizability of the review’s findings. Future reviews should consider the inclusion of non-English papers. Our search strategy was limited to publications and therefore excludes registries that were operationalized without any publications (e.g., local quality improvement or annual reports not published in the peer review literature). We retrospectively searched the grey literature where a registry that fulfilled the inclusion criteria was identified but was not the primary paper. One example of this is the World Health Organization’s clinical registry tool, a web-based platform for aggregation and analysis of case-based data from emergency care visits [91]. Most health service quality improvement projects and evaluations are contained within the service itself and therefore initiatives generated from registry data are not able to be quantified unless published in the peer review literature.
Some countries adopted a whole health system approach for clinical quality registries based around innovative implementation of health information management technology. Emergency department subsets of these large registries were excluded from our search strategy as they were not considered a feasible approach for many clinicians and clinician researchers considering developing and implementing an ED registry.
Finally, the practical implications of developing ED registries were unable to be explored given the paucity and variable literature available. A more focused area of ED registry analysis utilizing a systematic review methodology in the future should be undertaken to provide these insights.
6. Conclusions
The use of clinical registries for quality improvement and research has grown significantly and will continue to do so with advancements in information technology. Whilst many registries are used to evaluate and enhance the quality of care provided, the chaotic nature of EDs has been overlooked. From our scoping review, internationally there appears to be a lack of published registries and secondary publications. Of those that do exist, ED-based airway registries have been the most abundant and can potentially serve as a ‘pilot’ registry for departments to understand capacity and capability for managing and using registry data. Funding appears to be a primary barrier to success. The establishment of comprehensive general ED registries presents an opportunity to evaluate care quality. By integrating these registries within a learning health system framework, clinicians can adopt a proactive, quality-centered approach to community healthcare, moving beyond the current reactive and safety-oriented model.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/healthcare13091022/s1, Table S1: Preferred Reporting Items for Systematic reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) Checklist; Table S2: Aims, results and conclusion of primary ED registry publications specific for a condition or population; Table S3: Aims, results, and conclusion of studies secondary publications (both general scope and specific for a condition or population).
Author Contributions
Conceptualization, V.T.; methodology, V.T., S.P. and G.B.; formal analysis, V.T. and S.P.; investigation, V.T., S.P. and G.B; resources, V.T., S.P. and G.B; data curation, V.T., S.P. and G.B; writing—original draft preparation, V.T.; writing—review and editing, V.T., S.P. and G.B; visualization, V.T.; supervision, V.T.; project administration, G.B.; funding acquisition, V.T., S.P. and G.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research and the APC was funded by the Medical Research Future Fund (MRFF), grant number MRF2018041.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in the study are included in the publication/Supplementary Material; further inquiries can be directed to the corresponding author/s.
Conflicts of Interest
The authors declare no conflicts of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Appendix A. Search Strategy
The following electronic databases were searched: National Library of Medicine via PubMed, Embase, and Web of Science as a minimum requirement to guarantee adequate and efficient coverage (Table A1) [22]. The search period included date of database inception to April 2024. For all databases, only publications in English and where full text was available were included.
For the National Library of Medicine, the PubMed Central search field query entered was: (((registry[Title]) OR register[Title]) OR database[Title]) AND emergency[Title]. For embase, we used emtree terms; ‘registry’ or ‘register’ or ‘database’ combined with the MeSH terms referring to ‘emergency ward’ or ‘emergency medicine’ or ‘emergency care’. For the Web of Science we searched in “All Databases”, “All” collections, document type ‘article’, language English. We used the search terms: (((SO = (emergency)) AND SO = (registry)) OR SO = (register)) OR SO = (database).
Medical Subject Headings (MeSH), ‘registries’ or ‘database’ AND ‘emergency medicine’ or ‘emergency room visits’ or ‘emergency medical service’ or ‘evidence based emergency medicine’.
Table A1.
Detailed search strategy for PubMed, Embase, and Web of Science.
References
- Trzeciak, S.; Rivers, E.P. Emergency Department Overcrowding in the United States: An Emerging Threat to Patient Safety and Public Health. Emerg. Med. J. 2003, 20, 402–405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tran, V.; Barrington, G.; Page, S. The Tasmanian Emergency Care Outcomes Registry (TECOR) Protocol. Emerg. Care Med. 2024, 1, 153–164. [Google Scholar] [CrossRef] [Scilit]
- Schneider, S.M.; Gardner, A.F.; Weiss, L.D.; Wood, J.P.; Ybarra, M.; Beck, D.M.; Stauffer, A.R.; Wilkerson, D.; Brabson, T.; Jennings, A.; et al. The Future of Emergency Medicine. J. Emerg. Nurs. 2010, 36, 330–335. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sprivulis, P.C.; Da Silva, J.-A.; Jacobs, I.G.; Frazer, A.R.L.; Jelinek, G.A. The Association Between Hospital Overcrowding and Mortality Among Patients Admitted via Western Australian Emergency Departments. Med. J. Aust. 2006, 184, 208–212. [Google Scholar] [CrossRef] [Scilit]
- Ramlakhan, S.; Qayyum, H.; Burke, D.; Brown, R. The Safety of Emergency Medicine. Emerg. Med. J. 2016, 33, 293–299. [Google Scholar] [CrossRef] [Scilit]
- Gliklich, R.E.; Dreyer, N.A.; Leavy, M.B. Registries for Evaluating Patient Outcomes: A User’s Guide, 4th ed.; AHRQ Methods for Effective Health Care: Rockville, MD, USA, 2020; pp. 8–27. [Google Scholar]
- Evans, S.M.; Scott, I.A.; Johnson, N.P.; Cameron, P.A.; McNeil, J.J. Development of Clinical-Quality Registries in Australia: The Way Forward. Med. J. Aust. 2011, 194, 360–363. [Google Scholar] [CrossRef] [Scilit]
- Secombe, P.; Millar, J.; Litton, E.; Chavan, S.; Hensman, T.; Hart, G.K.; Slater, A.; Herkes, R.; Huckson, S.; Pilcher, D.V. Thirty Years of ANZICS CORE: A Clinical Quality Success Story. Crit. Care Resusc. 2023, 25, 43–46. [Google Scholar] [CrossRef] [Scilit]
- Gong, J.; Singer, Y.; Cleland, H.; Wood, F.; Cameron, P.; Tracy, L.M.; Gabbe, B.J. Driving Improved Burns Care and Patient Outcomes Through Clinical Registry Data: A Review of Quality Indicators in the Burns Registry of Australia and New Zealand. Burns. 2021, 47, 14–24. [Google Scholar] [CrossRef] [Scilit]
- Australian Commission on Safety and Quality in Health Care. Australian Framework for National Clinical Quality Registries. Available online: https://www.safetyandquality.gov.au/publications-and-resources/resource-library/australian-framework-national-clinical-quality-registries-2024 (accessed on 6 March 2025).
- Australian Commission on Safety and Quality in Health Care. Australian Register of Clinical Registries. Available online: https://www.safetyandquality.gov.au/publications-and-resources/australian-register-clinical-registries (accessed on 27 March 2024).
- National Institutes of Health. List of Registries. Available online: https://www.nih.gov/health-information/nih-clinical-research-trials-you/list-registries (accessed on 11 December 2024).
- Etkin, C.D.; Springer, B.D. The American Joint Replacement Registry—The First 5 Years. Arthroplasty Today 2017, 3, 67–69. [Google Scholar] [CrossRef] [Scilit]
- Gómez-Bueno, M.; Pérez de la Sota, E.; Forteza Gil, A.; Ortiz-Berbel, D.; Castrodeza, J.; García-Cosío Carmena, M.D.; Barge-Caballero, E.; Rangel Sousa, D.; Díaz Molina, B.; Manrique Antón, R.; et al. Durable ventricular assist device in Spain (2007–22020). First report of the REGALAD registry. Rev. Esp. Cardiol. (Engl. Ed.) 2023, 76, 227–237. [Google Scholar] [CrossRef] [Scilit]
- Wennergren, D.; Ekholm, C.; Sandelin, A.; Möller, M. The Swedish Fracture Register: 103,000 Fractures Registered. BMC Musculoskelet. Disord. 2015, 16, 338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cadilhac, D.A.; Kim, J.; Lannin, N.A.; Kapral, M.K.; Schwamm, L.H.; Dennis, M.S.; Norrving, B.; Meretoja, A. National Stroke Registries for Monitoring and Improving the Quality of Hospital Care: A Systematic Review. Int. J. Stroke. 2015, 11, 28–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cameron, P.A.; Fitzgerald, M.C.; Curtis, K.; McKie, E.; Gabbe, B.; Earnest, A.; Christey, G.; Clarke, C.; Crozier, J.; Dinh, M.; et al. Over View of Major Traumatic Injury in Australia––Implications for Trauma System Design. Injury 2020, 51, 114–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Craig, S.; O’Reilly, G.M.; Egerton-Warburton, D.; Jones, P.; Than, M.P.; Tran, V.; Taniar, D.; Moore, K.; Alvandi, A.; Tuxen-Vu, J.; et al. Making the Most of What We Have: What Does the Future Hold for Emergency Department Data? Emerg. Med. Australas. 2024, 36, 795–798. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Peters, M.D.J.; Marnie, C.; Tricco, A.C.; Pollock, D.; Munn, Z.; Alexander, L.; McInerney, P.; Godfrey, C.M.; Khalil, H. Updated Methodological Guidance for the Conduct of Scoping Reviews. JBI Evid. Synth. 2020, 18, 2119–2126. [Google Scholar] [CrossRef] [Scilit]
- McGowan, J.; Sampson, M.; Salzwedel, D.M.; Cogo, E.; Foerster, V.; Lefebvre, C. PRESS Peer Review of Electronic Search Strategies: 2015 Guideline Statement. J. Clin. Epidemiol. 2016, 75, 40–46. [Google Scholar] [CrossRef] [Scilit]
- Bramer, W.M.; Rethlefsen, M.L.; Kleijnen, J.; Franco, O.H. Optimal Database Combinations for Literature Searches in Systematic Reviews: A Prospective Exploratory Study. Syst. Rev. 2017, 6, 245. [Google Scholar] [CrossRef] [Scilit]
- Williams, J.M.; Greenslade, J.H.; McKenzie, J.V.; Chu, K.H.; Brown, A.; Paterson, D.; Lipman, J. A Prospective Registry of Emergency Department Patients Admitted with Infection. BMC Infect. Dis. 2011, 11, 27. [Google Scholar] [CrossRef] [Scilit]
- Venkatesh, A.; Ravi, S.; Rothenberg, C.; Kinsman, J.; Sun, J.; Goyal, P.; Augustine, J.; Epstein, S.K. Fair Play: Application of Normalized Scoring to Emergency Department Throughput Quality Measures in a National Registry. Ann. Emerg. Med. 2021, 77, 501–510. [Google Scholar] [CrossRef] [Scilit]
- Van Oeveren, L.; Donner, J.; Fantegrossi, A.; Mohr, N.M.; Brown, C.A., 3rd. Telemedicine-Assisted Intubation in Rural Emergency Departments: A National Emergency Airway Registry Study. Telemed. J. E Health 2017, 23, 290–297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trent, S.A.; Kaji, A.H.; Carlson, J.N.; McCormick, T.; Haukoos, J.S.; Brown, C.A., 3rd; National Emergency Airway Registry Investigators. Video Laryngoscopy Is Associated with First-Pass Success in Emergency Department Intubations for Trauma Patients: A Propensity Score Matched Analysis of the National Emergency Airway Registry. Ann. Emerg. Med. 2021, 78, 708–719. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Theron, L.; Jansen, K.; Miles, J. Benzylpiperizine-Based Party Pills’ Impact on the Auckland City Hospital Emergency Department Overdose Database (2002–2004) Compared with Ecstasy (MDMA or Methylene Dioxymethamphetamine), Gamma Hydroxybutyrate (GHB), Amphetamines, Cocaine, and Alcohol. N. Z. Med. J. 2007, 120, U2416. [Google Scholar] [PubMed]
- Stoecklein, H.H.; Kelly, C.; Kaji, A.H.; Fantegrossi, A.; Carlson, M.; Fix, M.L.; Madsen, T.; Walls, R.M.; Brown, C.A., 3rd; NEAR Investigators. Multicenter Comparison of Nonsupine Versus Supine Positioning During Intubation in the Emergency Department: A National Emergency Airway Registry (NEAR) Study. Acad. Emerg. Med. 2019, 26, 1144–1151. [Google Scholar] [CrossRef] [Scilit]
- Sandefur, B.J.; Liu, X.W.; Kaji, A.H.; Campbell, R.L.; Driver, B.E.; Walls, R.M.; Carlson, J.N.; Brown, C.A., 3rd; National Emergency Airway Registry Investigators. Emergency Department Intubations in Patients with Angioedema: A Report from the National Emergency Airway Registry. J. Emerg. Med. 2021, 61, 481–488. [Google Scholar] [CrossRef] [Scilit]
- Sacchetti, A.; Senula, G.; Strickland, J.; Dubin, R. Procedural Sedation in the Community Emergency Department: Initial Results of the ProSCED Registry. Acad. Emerg. Med. 2007, 14, 41–46. [Google Scholar] [CrossRef] [Scilit]
- Sacchetti, A.; Stander, E.; Ferguson, N.; Maniar, G.; Valko, P. Pediatric Procedural Sedation in the Community Emergency Department: Results from the ProSCED Registry. Pediatr. Emerg. Care. 2007, 23, 218–222. [Google Scholar] [CrossRef] [Scilit]
- Ruderman, B.T.; Mali, M.; Kaji, A.H.; Kilgo, R.; Watts, S.; Wells, R.; Limkakeng, A.T.; Borawski, J.B.; Fantegrossi, A.E.; Walls, R.M.; et al. Direct vs Video Laryngoscopy for Difficult Airway Patients in the Emergency Department: A National Emergency Airway Registry Study. West. J. Emerg. Med. 2022, 23, 706–715. [Google Scholar] [CrossRef] [Scilit]
- Pollack, C.V.; Schreiber, D.; Goldhaber, S.Z.; Slattery, D.; Fanikos, J.; O’Neil, B.J.; Thompson, J.R.; Hiestand, B.; Briese, B.A.; Pendleton, R.C.; et al. Clinical Characteristics, Management, and Outcomes of Patients Diagnosed with Acute Pulmonary Embolism in the Emergency Department: Initial Report of EMPEROR (Multicenter Emergency Medicine Pulmonary Embolism in the Real World Registry). J. Am. Coll. Cardiol. 2011, 57, 700–706. [Google Scholar] [CrossRef] [Scilit]
- Phelan, M.P.; Glauser, J.; Yuen, H.W.; Sturges-Smith, E.; Schrump, S.E. Airway Registry: A Performance Improvement Surveillance Project of Emergency Department Airway Management. Am. J. Med. Qual. 2010, 25, 346–350. [Google Scholar] [CrossRef] [Scilit]
- Davies, S.J.D.; Grundmeier, R.W.; Campos, D.A.; Hayes, K.L.; Bell, J.; Alessandrini, E.A.; Bajaj, L.; Chamberlain, J.M.; Gorelick, M.H.; Enriquez, R.; et al. The Pediatric Emergency Care Applied Research Network Registry: A Multicentre Electronic Health Record Registry of Pediatric Emergency Care. Appl. Clin. Inform. 2018, 9, 366–376. [Google Scholar] [CrossRef] [Scilit]
- Pallin, D.J.; Dwyer, R.C.; Walls, R.M.; Brown, C.A., 3rd; NEAR III Investigators. Techniques and Trends, Success Rates, and Adverse Events in Emergency Department Pediatric Intubations: A Report from the National Emergency Airway Registry. Ann. Emerg. Med. 2016, 67, 610–615.e611. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Otto, R.; Blaschke, S.; Schirrmeister, W.; Drynda, S.; Walcher, F.; Greiner, F. Length of Stay as Quality Indicator in Emergency Departments: Analysis of Determinants in the German Emergency Department Data Registry (AKTIN Registry). Intern. Emerg. Med. 2022, 17, 1199–1209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Offenbacher, J.; Nikolla, D.A.; Carlson, J.N.; Smith, S.W.; Genes, N.; Boatright, D.H.; Brown, C.A., 3rd. Incidence of Rescue Surgical Airways After Attempted Orotracheal Intubation in the Emergency Department: A National Emergency Airway Registry (NEAR) Study. Am. J. Emerg. Med. 2023, 68, 22–27. [Google Scholar] [CrossRef] [Scilit]
- O’Reilly, G.M.; Mitchell, R.D.; Mitra, B.; Noonan, M.P.; Hiller, R.; Brichko, L.; Luckhoff, C.; Paton, A.; Smit, V.; Cameron, P.A. Impact of Patient Isolation on Emergency Department Length of Stay: A Retrospective Cohort Study Using the Registry for Emergency Care. Emerg. Med. Australas. 2020, 32, 1034–1039. [Google Scholar] [CrossRef] [Scilit]
- Nikolla, D.A.; Offenbacher, J.; Smith, S.W.; Genes, N.G.; Herrera, O.A.; Carlson, J.N.; Brown, C.A., 3rd. First-Attempt Success Between Anatomically and Physiologically Difficult Airways in the National Emergency Airway Registry. Anesth. Analg. 2024, 138, 1249–1259. [Google Scholar] [CrossRef] [Scilit]
- Miró, Ò.; Martínez, G.; Masip, J.; Gil, V.; Martín-Sánchez, F.J.; Llorens, P.; Herrero-Puente, P.; Sánchez, C.; Richard, F.; Lucas-Invernón, J.; et al. Effects on Short Term Outcome of Non-Invasive Ventilation Use in the Emergency Department To Treat Patients With Acute Heart Failure: A Propensity Score-Based Analysis of the EAHFE Registry. Eur. J. Intern. Med. 2018, 53, 45–51. [Google Scholar] [CrossRef] [Scilit]
- Miró, Ò.; Llorens, P.; Freund, Y.; Davison, B.; Takagi, K.; Herrero-Puente, P.; Jacob, J.; Martín-Sánchez, F.J.; Gil, V.; Rosselló, X.; et al. Early Intravenous Nitroglycerin Use in Prehospital Setting and in the Emergency Department to Treat Patients with Acute Heart Failure: Insights from the EAHFE Spanish Registry. Int. J. Cardiol. 2021, 344, 127–134. [Google Scholar] [CrossRef] [Scilit]
- Mendez, J.; Escandon, M.; Tapia, A.D.; Davis, W.T.; April, M.D.; Maddry, J.K.; Couperus, K.; Hu, J.S.; Chin, E.; Schauer, S.G. Development of the Defense Registry for Emergency Airway Management (DREAM). Med. J. (Fort Sam Houst. Tex.) 2021, PB 8-21-04/05/06, 93–97. [Google Scholar]
- McCain, J.E.; Bridgmon, A.E.; King, W.D.; Monroe, K. Children’s Injury Database: Development of an Injury Surveillance System in a Pediatric Emergency Department. Inj. Epidemiol. 2023, 10, 40. [Google Scholar] [CrossRef] [Scilit]
- Llorens, P.; Escoda, R.; Miró, Ò.; Herrero-Puente, P.; Martín-Sánchez, F.J.; Jacob, J.; Garrido, J.M.; Pérez-Durá, M.J.; Gil, C.; Fuentes, M.; et al. Characteristics and Clinical Course of Patients With Acute Heart Failure and the Therapeutic Measures Applied in Spanish Emergency Departments: Based on the EAHFE Registry (Epidemiology of Acute Heart Failure in Emergency Departments). Emergencias 2015, 27, 11–22. [Google Scholar] [PubMed]
- Lin, B.W.; Schreiber, D.H.; Liu, G.; Briese, B.; Hiestand, B.; Slattery, D.; Kline, J.A.; Goldhaber, S.Z.; Pollack, C.V., Jr. Therapy and Outcomes in Massive Pulmonary Embolism from the Emergency Medicine Pulmonary Embolism in the Real World Registry. Am. J. Emerg. Med. 2012, 30, 1774–1781. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ekelund, U.; Kurland, L.; Eklund, F.; Torkki, P.; Letterstål, A.; Lindmarker, P.; Castrén, M. Patient Throughput Times and Inflow Patterns in Swedish Emergency Departments. A Basis for ANSWER, A National SWedish Emergency Registry. Scand. J. Trauma, Resusc. Emerg. Med. 2011, 19, 37. [Google Scholar] [CrossRef] [Scilit]
- Lassen, A.T.; Jørgensen, H.; Jørsboe, H.B.; Odby, A.; Brabrand, M.; Steinmetz, J.; Mackenhauer, J.; Kirkegaard, H.; Christiansen, C.F. The Danish Database for Acute and Emergency Hospital Contacts. Clin. Epidemiol. 2016, 8, 469–474. [Google Scholar] [CrossRef] [Scilit]
- Brown, C.A.; Bair, A.E.; Pallin, D.J.; Walls, R.M.; Investigators, N.I. Techniques, Success, and Adverse Events of Emergency Department Adult Intubations. Ann. Emerg. Med. 2015, 65, 363–370.e1. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.; Kim, S.; You, J.S.; Choi, H.J.; Chung, H.S. The Clinical Effectiveness of Simulation Based Airway Management Education Using the Korean Emergency Airway Registry. Signa Vitae 2017, 13, 56–60. [Google Scholar] [CrossRef] [Scilit]
- Khalil, A.A.; El-Setouhy, M.; Hirshon, J.M.; El-Shinawi, M. Developing a Trauma Registry for the Emergency Department of a Tertiary Care Hospital in Egypt: A Step Toward Success. Egypt. J. Surg. 2021, 40, 649–655. [Google Scholar]
- Kaisler, M.C.; Hyde, R.J.; Sandefur, B.J.; Kaji, A.H.; Campbell, R.L.; Driver, B.E.; Brown, C.A., 3rd. Awake Intubations in the Emergency Department: A Report from the National Emergency Airway Registry. Am. J. Emerg. Med. 2021, 49, 48–51. [Google Scholar] [CrossRef] [Scilit]
- Jimenez, S.; Ruiz-Artacho, P.; Merlo, M.; Suero, C.; Antolin, A.; Casal, J.R.; Sanchez, M.; Ortega-Duarte, A.; Genis, M.; Piñera, P. Risk Profile, Management, and Outcomes of Patients with Venous Thromboembolism Attended in Spanish Emergency Departments: The ESPHERIA Registry. Medicine 2017, 96, e8796. [Google Scholar] [CrossRef] [Scilit]
- Jeong, J.; Kim, Y.J.; Kong, S.Y.; Shin, S.D.; Ro, Y.S.; Wi, D.H.; Kim, S.C.; Sun, K.M.; Kim, S.; Kang, S.B.; et al. Monitoring of Characteristics of the Patients Visiting an Emergency Center in Cameroon Through the Development of Hospital Patient Database. Afr. J. Emerg. Med. 2022, 12, 77–84. [Google Scholar] [CrossRef] [Scilit]
- Jacob, J.; Cabello, I.; Yuguero, O.; Alexis Guzmán, J.; Arranz Betegón, M.; Abadías, M.J.; Francés Artigas, P.; Santos, J.; Esquerrà, A.; Mòdol, J.M. Emergency Atrial Fibrillation Registry of the Catalan Institute of Health (URGFAICS): Analysis by Type of Atrial Fibrillation and Revisits Within 30 Days. Emergencias. 2019, 31, 99–106. [Google Scholar] [PubMed]
- Hart, J.C.; Goldstein, L.N. Analysis of the Airway Registry from an Academic Emergency Department in South Africa. S. Afr. Med. J. 2020, 110, 484–490. [Google Scholar] [PubMed]
- Hansen, K.; Schultz, T.; Crock, C.; Deakin, A.; Runciman, W.; Gosbell, A. The Emergency Medicine Events Register: An Analysis of the First 150 Incidents Entered into a Novel, Online Incident Reporting Registry. Emerg. Med. Australas. 2016, 28, 544–550. [Google Scholar] [CrossRef] [Scilit]
- Alonso, C.F.; Avilés, R.A.; López, M.L.; Martínez, F.G.; Ferrer, M.F.; Bañeres, B.G.; Najera, D.; Loaiza, J.E.G.; García, L.B.Z. Differences in Emergency Department Care of Adults with a First Epileptic Seizure Versus a Recurrent Seizure: A Study of the ACESUR (Acute Epileptic Seizures in the Emergency Department) Registry. Emergencias 2019, 31, 91–98. [Google Scholar]
- Garcia, S.I.; Sandefur, B.J.; Campbell, R.L.; Driver, B.E.; April, M.D.; Carlson, J.N.; Walls, R.M.; Brown, C.A., 3rd. First-Attempt Intubation Success Among Emergency Medicine Trainees by Laryngoscopic Device and Training Year: A National Emergency Airway Registry Study. Ann. Emerg. Med. 2023, 81, 649–657. [Google Scholar] [CrossRef] [Scilit]
- Fogg, T.; Alkhouri, H.; Vassiliadis, J. The Royal North Shore Hospital Emergency Department Airway Registry: Closing the Audit Loop. Emerg. Med. Australas. 2016, 28, 27–33. [Google Scholar] [CrossRef] [Scilit]
- Ferguson, I.; Alkhouri, H.; Fogg, T.; Aneman, A. Ketamine Use for Rapid Sequence Intubation in Australian and New Zealand Emergency Departments From 2010 to 2015: A Registry Study. Emerg. Med. Australas. 2019, 31, 205–210. [Google Scholar] [CrossRef] [Scilit]
- Chong, S.L.; Barbier, S.; Liu, N.; Ong, G.Y.; Ng, K.C.; Ong, M.E. Predictors for Moderate to Severe Paediatric Head Injury Derived from a Surveillance Registry in the Emergency Department. Injury 2015, 46, 1270–1274. [Google Scholar] [CrossRef] [Scilit]
- Choi, H.J.; Je, S.M.; Kim, J.H.; Kim, E. The Factors Associated with Successful Paediatric Endotracheal Intubation on the First Attempt in Emergency Departments: A 13-Emergency-Department Registry Study. Resuscitation 2012, 83, 1363–1368. [Google Scholar] [CrossRef] [Scilit]
- Choi, D.; Park, J.W.; Kwak, Y.H.; Kim, D.K.; Jung, J.Y.; Lee, J.H.; Jung, J.H.; Suh, D.; Lee, H.N.; Lee, E.J.; et al. Comparison of Age-Adjusted Shock Indices as Predictors of Injury Severity in Paediatric Trauma Patients Immediately After Emergency Department Triage: A Report from the Korean Multicentre Registry. Injury 2024, 55, 111108. [Google Scholar] [CrossRef] [Scilit]
- Cho, J.; Cho, Y.S.; You, J.S.; Lee, H.S.; Kim, H.; Chung, H.S. Current Status of Emergency Airway Management for Elderly Patients in Korea: Multicentre Study Using the Korean Emergency Airway Management Registry. Emerg. Med. Australas. 2013, 25, 439–444. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chan, G.W.H.; Chai, C.Y.; Teo, J.S.Y.; Tjio, C.K.E.; Chua, M.T.; Brown, I.C. Emergency Airway Management in a Singapore Centre: A Registry Study. Ann. Acad. Med. Singap. 2021, 50, 42–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carriel Mancilla, J.; Jiménez Hernández, S.; Martín-Sánchez, F.J.; Jiménez, D.; Fuentes Ferrer, M.; Ruiz-Artacho, P. Clinical Characteristics and Course in Emergency Department Patients with Chronic Obstructive Pulmonary Disease and Symptomatic Acute Venous Thromboembolic Disease: Secondary Analysis of the ESPHERIA Registry. Emergencias 2020, 32, 40–44. [Google Scholar] [PubMed]
- Carriel Mancilla, J.; Jiménez Hernández, S.; Martín-Sánchez, F.J.; Jiménez, D.; Lecumberri, R.; Alonso Valle, H.; Beddar Chaib, F.; Ruiz-Artacho, P. Profiles of Patients with Venous Thromboembolic Disease in the Emergency Department and Their Medium-Term Prognosis: Data from the ESPHERIA Registry. Emergencias 2021, 33, 107–114. [Google Scholar]
- Cabello, I.; Jacob, J.; Arranz, M.; Yuguero, O.; Guzman, J.; Moreno-Pena, A.; Frances, P.; Santos, J.; Esquerrà, A.; Mòdol, J.M. Impact of Emergency Department Management of Atrial Fibrillation with Amiodarone on Length of Stay. A Propensity Score Analysis Based on the URGFAICS Registry. Eur. J. Emerg. Med. 2020, 27, 429–435. [Google Scholar] [CrossRef] [Scilit]
- Brown, C.A., 3rd; Kaji, A.H.; Fantegrossi, A.; Carlson, J.N.; April, M.D.; Kilgo, R.W.; Walls, R.M. Video Laryngoscopy Compared to Augmented Direct Laryngoscopy in Adult Emergency Department Tracheal Intubations: A National Emergency Airway Registry (NEAR) Study. Acad. Emerg. Med. 2020, 27, 100–108. [Google Scholar] [CrossRef] [Scilit]
- Bressan, S.; Da Dalt, L.; Chamorro, M.; Abarca, R.; Azzolina, D.; Gregori, D.; Sereni, F.; Montini, G.; Tognoni, G. Paediatric Emergencies and Related Mortality in Nicaragua: Results from a Multi-Site Paediatric Emergency Registry. Emerg. Med. J. 2021, 38, 338–344. [Google Scholar] [CrossRef] [Scilit]
- Bennett, S.; Alkhouri, H.; Badge, H.; Long, E.; Chan, T.; Vassiliadis, J.; Fogg, T. Bed Tilt and Ramp Positions Are Associated with Increased First-Pass Success of Adult Endotracheal Intubation in the Emergency Department: A Registry Study. Emerg. Med. Australas. 2023, 35, 983–990. [Google Scholar] [CrossRef] [Scilit]
- Beauchet, O.; Cooper-Brown, L.A.; Lubov, J.; Allali, G.; Afilalo, M.; Launay, C.P. “Emergency Room Evaluation and Recommendations” (ER2) Tool for the Screening of Older Emergency Department Visitors with Major Neurocognitive Disorders: Results from the ER2 Database. Front. Neurol. 2022, 12, 767285. [Google Scholar] [CrossRef] [Scilit]
- Barford, C.; Lauritzen, M.M.; Danker, J.K.; Sölétormos, G.; Berlac, P.A.; Lippert, F.; Lundstrøm, L.H.; Antonsen, K.; Lange, K.H. The Formation and Design of the ‘Acute Admission Database’- a Database Including a Prospective, Observational Cohort of 6279 Patients Triaged in the Emergency Department in a Larger Danish Hospital. Scand. J. Trauma. Resusc. Emerg. Med. 2012, 20, 29. [Google Scholar] [CrossRef] [Scilit]
- Balls, A.; LoVecchio, F.; Kroeger, A.; Stapczynski, J.S.; Mulrow, M.; Drachman, D. Ultrasound Guidance for Central Venous Catheter Placement: Results from the Central Line Emergency Access Registry Database. Am. J. Emerg. Med. 2010, 28, 561–567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arranz, M.; Jacob, J.; Sancho-Ramoneda, M.; Lopez, À.; Navarro-Sáez, M.C.; Cousiño-Chao, J.R.; López-Altimiras, X.; López, I.V.F.; García-Trallero, O.; German, A.; et al. Characteristics of Prolonged Noninvasive Ventilation in Emergency Departments and Impact Upon Effectiveness. Analysis of the VNICat Registry. Med. Intensiva. (Engl. Ed.) 2021, 45, 477–484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- April, M.D.; Schauer, S.G.; Brown Rd, C.A.; Ng, P.C.; Fernandez, J.; Fantegrossi, A.E.; Maddry, J.K.; Summers, S.; Sessions, D.J.; Barnwell, R.M.; et al. A 12-Month Descriptive Analysis of Emergency Intubations at Brooke Army Medical Center: A National Emergency Airway Registry Study. US Army Med. Dep. J. 2017, 3–17, 98–104. [Google Scholar]
- April, M.D.; Driver, B.; Schauer, S.G.; Carlson, J.N.; Bridwell, R.E.; Long, B.; Stang, J.; Farah, S.; De Lorenzo, R.A.; Brown, C.A., 3rd. Extraglottic Device Use Is Rare During Emergency Airway Management: A National Emergency Airway Registry (NEAR) Study. Am. J. Emerg. Med. 2023, 72, 95–100. [Google Scholar] [CrossRef] [Scilit]
- April, M.D.; Arana, A.; Schauer, S.G.; Davis, W.T.; Oliver, J.J.; Fantegrossi, A.; Summers, S.M.; Maddry, J.K.; Walls, R.M.; Brown, C.A., 3rd. Ketamine Versus Etomidate and Peri-Intubation Hypotension: A National Emergency Airway Registry Study. Acad. Emerg. Med. 2020, 27, 1106–1115. [Google Scholar] [CrossRef] [Scilit]
- April, M.D.; Arana, A.; Reynolds, J.C.; Carlson, J.N.; Davis, W.T.; Schauer, S.G.; Oliver, J.J.; Summers, S.M.; Long, B.; Walls, R.M.; et al. Peri-intubation cardiac arrest in the Emergency Department: A National Emergency Airway Registry (NEAR) study. Resuscitation 2021, 162, 403–411. [Google Scholar] [CrossRef] [Scilit]
- April, M.D.; Arana, A.; Pallin, D.J.; Schauer, S.G.; Fantegrossi, A.; Fernandez, J.; Maddry, J.K.; Summers, S.M.; Antonacci, M.A.; Brown, C.A., 3rd. Emergency Department Intubation Success with Succinylcholine Versus Rocuronium: A National Emergency Airway Registry Study. Ann. Emerg. Med. 2018, 72, 645–653. [Google Scholar] [CrossRef] [Scilit]
- Alkhouri, H.; Richards, C.; Miers, J.; Fogg, T.; McCarthy, S. Case Series and Review of Emergency Front-of-Neck Surgical Airways from the Australian and New Zealand Emergency Department Airway Registry. Emerg. Med. Australas. 2021, 33, 499–507. [Google Scholar] [CrossRef] [Scilit]
- Af Ugglas, B.; Lindmarker, P.; Ekelund, U.; Djärv, T.; Holzmann, M.J. Emergency Department Crowding and Mortality in 14 Swedish Emergency Departments, a Cohort Study Leveraging the Swedish Emergency Registry (SVAR). PLoS ONE 2021, 16, e0247881. [Google Scholar] [CrossRef] [Scilit]
- Alkhouri, H.; Vassiliadis, J.; Murray, M.; Mackenzie, J.; Tzannes, A.; McCarthy, S.; Fogg, T. Emergency Airway Management in Australian and New Zealand Emergency Departments: A Multicentre Descriptive Study of 3710 Emergency Intubations. Emerg. Med. Australas. 2017, 29, 499–508. [Google Scholar] [CrossRef] [Scilit]
- Jawad, I.; Rashan, S.; Sigera, C.; Salluh, J.; Dondorp, A.M.; Haniffa, R.; Beane, A. A Scoping Review of Registry Captured Indicators for Evaluating Quality of Critical Care in ICU. J. Intensive Care 2021, 9, 48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Australian Commission on Safety and Quality in Health Care. Economic Evaluation of Clinical Quality Registries, Final Report. Available online: https://www.safetyandquality.gov.au/sites/default/files/migrated/Economic-evaluation-of-clinical-quality-registries-Final-report-Nov-2016.pdf (accessed on 5 March 2025).
- Lee, P.; Chin, K.; Liew, D.; Stub, D.; Brennan, A.L.; Lefkovits, J.; Zomer, E. Economic Evaluation of Clinical Quality Registries: A Systematic Review. BMJ Open 2019, 9, e030984. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palmer, C.S.; Davey, T.M.; Mok, M.T.; McClure, R.J.; Farrow, N.C.; Gruen, R.L.; Pollard, C.W. Standardising Trauma Monitoring: The Development of a Minimum Dataset for Trauma Registries in Australia and New Zealand. Injury 2013, 44, 834–841. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- National Institutes of Health. Institute of Medicine Roundtable on Evidence-Based Medicine. In The Learning Healthcare System: Workshop Summary; Olsen, L., Aisner, D., McGinnis, J.M., Eds.; National Academies Press (US), National Academy of Sciences: Washington, DC, USA, 2007. [Google Scholar]
- Pomare, C.; Mahmoud, Z.; Vedovi, A.; Ellis, L.A.; Knaggs, G.; Smith, C.L.; Zurynski, Y.; Braithwaite, J. Learning Health Systems: A Review of Key Topic Areas and Bibliometric Trends. Learn. Health Syst. 2022, 6, e10265. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. WHO Clinical Registry. Available online: https://www.who.int/publications/m/item/who-clinical-registry (accessed on 5 March 2025).

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).