


Abstract
Background: Cardiovascular diseases (CVDs) are associated with very high rates of re-hospitalization and mortality worldwide, so the complexity of these pathologies requires frequent access to hospital facilities. The guidelines also emphasize the importance of cardiac rehabilitation (CR) programs, which have demonstrated a favorable effect on outcomes, and cardiac telerehabilitation (CTR) could represent an innovative healthcare delivery model. The aim of our review is to study how technologies used in rehabilitation have changed over time and also to understand what types of rehabilitation programs have been used in telerehabilitation. Methods: We searched randomized controlled trials (RCTs) in three electronic databases, PubMed, Web of Science, and Scopus, from January 2015 to January 2024, using relevant keywords. Initially, 502 articles were found, and 79 duplicates were identified and eliminated with EndNote. Results: In total, 16 RCTs fulfilled the pre-defined criteria, which were analyzed in our systematic review. The results showed that after CTR, there was a significant improvement in main outcome measures, as well as in relation to technological advances. Conclusions: Moreover, compared to center-based rehabilitation, CTR can offer further advantages, with better cost-effectiveness, the breakdown of geographical barriers, and the improvement of access to treatment for the female population, which is traditionally more socially committed.
1. Introduction
Among chronic diseases, cardiovascular diseases (CVDs) are associated with very high rates of re-hospitalization and mortality worldwide. The complexity of these pathologies requires frequent access to hospital facilities in order to allow multidisciplinary assessments and for the execution of diagnostic tests, resulting in increased direct and indirect costs (loss of work days, travel, inappropriate hospitalizations) [1]. Moreover, technological evolution and the experiences gained during the COVID-19 emergency have shown the need to develop new organizational models based on the management of patients with CVD in telemedicine. The use of these technologies allows the patient to be taken in and supervised at home, allowing for a rehabilitation program to be conducted remotely and safely.
In order to reduce hospitalizations and improve the prognosis and the quality of life of CVD patients, especially with heart failure (HF), the recent guidelines [2,3] indicate the need for drug therapy based on four pharmacological “pillars” (Angiotensin-Converting Enzyme inhibitors—ACE inhibitors; Angiotensin Receptor Blocker—ARB; Angiotensin Receptor–Neprilysin Inhibitor—ARNI; mineralocorticoid receptor antagonists—MRA; beta blocker; Sodium–Glucose Cotransporter 2—SGLT2 inhibitors).
However, the international guidelines also emphasize the importance of cardiac rehabilitation (CR), which is an active and dynamic multifactorial process that includes exercise training, cardiac risk factor modification, psychosocial assessment, and outcome assessment [4], which have demonstrated favorable effects on clinical stability, reducing disability and the risk of subsequent cardiovascular events, supporting the maintenance and resumption of an active role in society, and improving survival and quality of life [5]. Consequently, CR and supervised training may be considered the fifth pillar in HF treatment [6], and the beneficial effects are evident in patients who adhere to long-term CR programs [7,8]. Unfortunately, despite much evidence, supervised training and CR programs are underestimated and underutilized [9], especially due to geographical social barriers and clinical conditions. Long-term participation and adherence to these programs should, therefore, be encouraged and strengthened. Telerehabilitation and mHealth can help to achieve this goal, as suggested in the international guidelines [10]. Telerehabilitation is a branch of telemedicine [11] in which information and communication technologies (ICTs) and, in advanced cases, remote-control technologies such as robotics are used to directly provide remote rehabilitation activities [12,13]. These technologies also include messaging and calls via telephone and/or the Internet, video conferencing communications between the patient and the healthcare provider, and sensor and telemonitoring systems [1]. In the case of telerehabilitation, the systems that allow information to be transmitted are as follows [14,15]:
- Hardware and software systems that acquire and process signals, images, and data;
- Applications that permit the transmission of health information in a bidirectional way;
- Dedicated web portals or information technology platforms.
In most cases, telerehabilitation is carried out by providing the patient with videos in which the exercises to be performed are shown. These exercises then can be performed either by videoconference with the therapist (“real-time” telerehabilitation, in which both the healthcare provider and the patient are online) or without supervision (in this case, however, the healthcare provider is “off-line”). In some cases, kits containing motion sensors, tablets with customized training software, and other peripherals can be provided to patients [16]. Telemedicine and all its components, including telerehabilitation, are recognized as relevant both nationally and internationally, so they are considered a “cultural revolution” [17]. This cultural revolution, however, is necessary because of the aging population and the resulting increased incidence of chronic diseases [18]. All of the above-mentioned indicate the need for innovative healthcare delivery models that support more patient-centered care in order to meet health needs more effectively, reducing current geographic gaps, ensuring a better “experience of care,” and improving the efficiency levels of healthcare systems through the promotion of home care and remote monitoring protocols [19]. Consequently, the aim of our review is to study how technologies used in rehabilitation have changed over time and also to understand what types of rehabilitation programs have been used in telerehabilitation.
2. Materials and Methods
2.1. Study Design
This systematic review was performed according to the Preferred Reporting Items for Systematic Review and Meta-Analyses (PRISMA) statement [20].
2.2. Literature Search
A literature analysis was performed to identify relevant studies in 3 electronic databases, PubMed, Web of Science (WOS), and Scopus, systematically searched from January 2015 to January 2024, taking into account only articles published in peer-reviewed journals, with the following keywords: (Cardiovascular Disease OR Disease, Cardiovascular OR Major Adverse Cardiac Events OR Cardiac Events OR Cardiac Event OR Event, Cardiac OR Adverse Cardiac Event OR Adverse Cardiac Events OR Cardiac Event, Adverse OR Cardiac Events, Adverse) AND (Telerehabilitation OR Tele-rehabilitation OR Tele rehabilitation OR Tele-rehabilitations OR Remote Rehabilitation). Complete search strategies are provided in Appendix A.
2.3. Inclusion and Criteria
In this review, we included articles published from January 2015 to January 2024 that were written in English language and had available full texts, along with studies targeting only humans that focused on telerehabilitation of patients with cardiovascular disease. We also defined and applied the following inclusion criteria to identify eligible papers: randomized controlled trials (RCTs) in which adults (≥18 years old) with CVD (i.e., myocardial infarction, angina, heart failure, or after revascularization) attend a cardiac telerehabilitation (CTR) program in comparison with a control group attending usual-care or center-based CR.
2.4. Study Selection
Before starting the article selection phase, duplicate records were removed with EndNote. After that, all articles were screened for title and abstract by two independent reviewers who separately selected and discussed conflicts about doubtful cases regarding the inclusion/exclusion criteria. Next, the review authors conducted full-text screening based on inclusion and exclusion criteria to determine the papers’ eligibility. During this process, if necessary, a third author resolved potential disagreements via discussion.
2.5. Risk of Bias and Quality Assessment of Studies
All the studies included are evaluated using the Cochrane risk-of-bias tool to assess the risk of all types of bias (selection bias, performance bias, attrition bias, reporting bias, and overall bias) [21] (Table 1). After that, all the studies were also checked for the Physiotherapy Evidence Database (PEDro) score to perform a quality assessment. The PEDro score [22] comprises 11 items, with a maximum of 10 points, because the first item (eligibility criteria) does not contribute to total score. Studies with a PEDro score of 9–10 points are considered excellent, studies with a score of 6–8 points are considered good, and, finally, studies with a score of ≤5 are considered poor (Table 2). Among the included studies, 10 are considered poor with a score of 4 or 5; the remaining 6 studies are considered good with a score between 6 and 8. None of the included studies are considered excellent.
Table 1.
Cochrane risk of bias tool for the risk of bias in individual studies.
Table 2.
Summary of PEDro scores for included studies. 1: eligibility criteria; 2: random allocation; 3: concealed allocation; 4: similarity at baseline; 5: subject blinding; 6: therapist blinding; 7: assessor blinding; 8: completeness of follow-up; 9: intention-to-treat analysis; 10: between-group statistical comparisons; 11: point measures and variability.
2.6. Data Extraction
Two of the reviewers (MG, AB) independently investigated the titles and abstracts extracted from the database searches to determine if they fit the inclusion criteria. Disagreements regarding the inclusion or exclusion of a particular manuscript based on the appraisal of its abstract were determined by reaching an agreement or consulting an additional reviewer (MC). Data extraction arrangements were established based on the current literature in the field and the research questions. Extraction of the data was based on essential information according to questions of the current review, such as (a) author, country, and year; (b) study design; (c) population; (d) diagnosis; (e) telerehabilitation; (f) control; (g) technological solutions; (h) outcomes; and (i) results (Table 3). In addition, for quicker reference, Table 4 shows the results of the studies and the qualitative assessment with the PEDro scale.
Table 3.
Descriptive characteristics of the included studies.
Table 4.
Results of the studies and the qualitative assessment with the PEDro scale.
3. Results
3.1. Study Selection and Characteristics
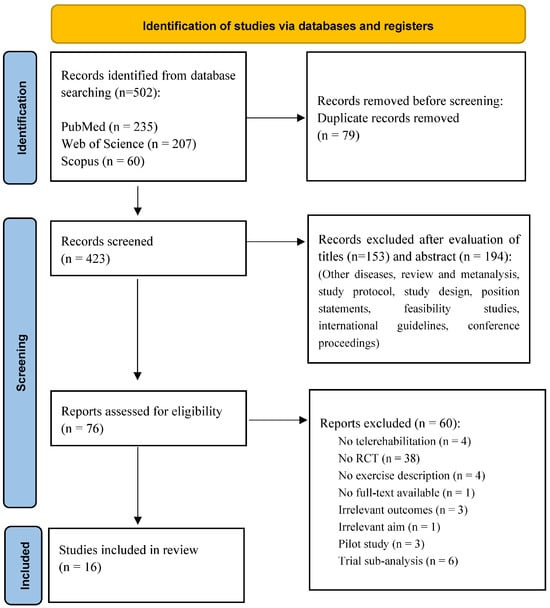
Initially, 502 articles were found through database searches on PubMed, WOS, and Scopus; after that, 79 duplicates were identified and eliminated with EndNote. A total of 423 articles were screened for titles and abstracts; after that, 76 papers were selected to be potentially relevant for the present review. Finally, 16 articles were included after full-text screening. This selection process is summarized in the PRISMA flow diagram (Figure 1), and in Table 3, there are the descriptive characteristics of the 16 studies included in the present review, with a focus on the study design, population, diagnosis, intervention, technological solution, measured outcomes, and results. Regarding the diseases assessed, twelve studies are about coronary artery diseases (CAD), one concerned patients with coexisting chronic obstructive pulmonary disease (COPD) and chronic heart failure (CHF), one concerned patients who underwent ablation for atrial fibrillation, and two concerned patients with HF.
Figure 1.
Flow diagram of study selection.
3.2. Monitoring Devices
The technological solutions adopted are the most varied and provide for the detection of vital parameters, which are transmitted in real-time by the device that detects them [24,25,27,33,35] or uploaded later by the patients using applications [23,26,34] in order to allow the safety of the patients during training and the monitoring of the correctness of the rehabilitation program. Some studies did not involve the detection of vital parameters but only the correct execution of movement by a sensor or with the use of virtual reality in CR [28,37,38]. Studies based on virtual reality do not generally aim to improve exercise tolerance but are aimed at anxiety and depression management [29,30]. In contrast, the study by Lima et al. [31], which also includes the use of virtual reality, is aimed at improving lung function in post-coronary artery bypass graft (CABG) patients. In the study conducted by Snoek et al. [36], the devices used are able to detect and transmit vital and exercise parameters in real time. Finally, in the 2015 study by Maddison et al., [32], there is no monitoring system; all outcome measures are based on patient’s self-reported data. In a 2020 study, on the other hand, the same authors use a very comprehensive system that can directly detect and transmit vital and movement parameters [33].
3.3. Intervention
As regards CR programs, the studies included in our review show a wide range of interventions, based mainly on exercise, sometimes accompanied by patient education on the management of risk factors (dietary interventions, cessation of smoking habits, maintenance of an active lifestyle) and counseling interventions for the management of anxiety and depression. These studies also show a wide range of rehabilitation programs in terms of types, intensity, and duration of exercise training. The rehabilitation programs mostly focus on exercise and range from a minimum of 6 weeks with a frequency of three times per week [27] to a maximum of 24 weeks [32,36,37,38] with a frequency ranging from three to five times per week.
In these studies, the exercise type is moderate-intensity aerobic training [32,36] alone or combined with strength training and stretching [37,38]. Three studies involve an 8-week home-based exercise program [25,34,35], which, in the case of Piotrowicz et al., 2020 [35], follows an initial 1-week center-based training. In all the above-mentioned studies, combined training, consisting of interval training exercises for strength training with TheraBand or calisthenics in addition to breathing exercises and endurance training (with an intensity ranging from 40 to 80% of the heart rate reserve (HRR)), is used.
Three studies provide a treatment duration of 12 weeks [23,26,33] with a frequency of at least three times or 150 min per week and an indication to be active at least 5 days per week. The exercise programs reported in these papers are based on endurance training at an intensity ranging from 40 to 80% of HRR. Only one study provides a personally tailored 16-week exercise program [24] with an intervention based on both endurance and resistance training, together with patient education about the desirability of maintaining a healthy lifestyle and practicing daily physical activity.
With regard to the studies including the use of virtual reality [29,30,31] associated with exercise training, there are generally only a few sessions, ranging from four to eight, aimed to improve symptoms such as anxiety and depression [29,30], which are often present in people with cardiovascular disease, or to enhance the respiratory pattern in post-CABG patients [31]. Despite the wide variety of rehabilitation programs proposed, we report the lack of studies involving exercises to improve flexibility and coordination, and only a few studies have included respiratory exercises.
3.4. Primary and Secondary Outcomes
As the primary outcome, most of the included studies consider cardiorespiratory fitness (CRF) assessed with cardiopulmonary exercise testing (CPET), expressed as peak oxygen consumption (VO2 peak) [23,26,32,34,36], maximal oxygen consumption (VO2 max) [33] or as metabolic equivalent of task (MET) [25]. Only two studies performed a 6-Minute Walking Test (6MWT) to evaluate the possible effects of CTR on exercise capacity [24,27]. The study by Frederix et al. is the only one that performs a cost analysis of CTR compared to center-based rehabilitation [28], while the two studies by Jozwik et al. take into account anxiety and depression levels assessed with the Hospital Anxiety and Depression Scale (HADS) [29,30].
As secondary outcomes in the studies analyzed, we mostly find assessments of physical activity, quality of life (QoL), training adherence, cardiovascular risk factors/laboratory parameters, and anxiety and depression levels. Physical activity is assessed in different ways, i.e., with the Physical Activity Scale for Elderly (PASE) [24], with the International Physical Activity Questionnaire (IPAQ) for the self-reported PA assessment [26,32,36], and finally, with the use of accelerometry data [28,33].
In several studies, QoL is also assessed, mainly with the Short Form 36 (SF-36) questionnaire [23,25,27,34,35]; two studies instead used the EuroQol five-dimensional (EQ5D) questionnaire for the evaluation of the QoL [32,33], whilst one study combined it with the Minnesota Living with Heart Failure Questionnaire (MLHFQ) [24].
Four studies also report an evaluation of treatment adherence [23,26,33,34] calculated according to the records provided by wearable devices like heart rate zones, accelerometers, and electrocardiogram (ECG) recording devices or through the compilation of exercise diaries.
The evaluations of cardiovascular risk factors/laboratory parameters like the anthropometric measures (body mass index, waist and hip circumferences), biochemical parameters (glucose, total cholesterol, low-density lipoprotein (LDL), high-density lipoprotein (HDL), cholesterol, triglycerides, glycated hemoglobin—HbA1c—and blood pressure) are reported in several studies included [25,33,36,37].
Finally, a psychological status evaluation was conducted using the Hospital Anxiety and Depression Scale (HADS) and the Patient Health Questionnaire (PHQ) [29,30,36]. Cai et al. also used the Health Beliefs Related to Cardiovascular Disease Scale and the Exercise Self-Efficacy Scale to evaluate the effects of CTR treatment on their patients.
4. Discussion
The aim of this review is to highlight how much telerehabilitation has changed since its beginnings. The technologies used in the included studies show a considerable evolution over time from simpler systems, such as text messages sent via telephone, to more sophisticated platforms, which are also equipped with virtual reality. In the studies dated between 2015 and 2018 [24,28,32], in fact, telerehabilitation was mostly designed as text messages, video messages, e-mails, and phone calls made by physiotherapists or nurses aimed to increase the exercise habits of the study participants; even in the 2015 study by Maddison et al., no patient monitoring system was provided [32].
In a 2019 paper published by the same authors [33], however, we also note a strong evolution of the telerehabilitation concept. In this study, in fact, telerehabilitation was delivered via the REMOTE-CR platform, one of the first platforms for telerehabilitation delivery, which was associated with a smartphone and sensors for the detection of vital parameters and movement that transmitted information in real time. Among the older studies, there are two [25,34] that already showed a different concept of telerehabilitation, very similar to how we understand it today, characterized, therefore, by personalized exercise programs monitored via devices integrated with web apps.
In addition to remote monitoring systems and platforms, there are also studies involving the use of virtual reality systems in CR with the aim of treating anxiety and depression and improving breathing quality [29,30,31]. Virtual reality in the management of such disorders is actually emerging as a very effective intervention, as it provides users with safe, non-threatening environments where patients can experience a different world and learn how to cope with their anxiety and depression [39]. These results are in line with the digitalization process in healthcare and are very encouraging as they go in the direction of overcoming the concept that technologies in rehabilitation deprive the patient of contact with the physiotherapist, on which the therapeutic relationship has always been based, and can therefore constitute a new and equally effective way of treating the patient as a whole [12,40,41].
Another aim of this review is to show what type of rehabilitation program have been mainly used in telerehabilitation and to highlight the effectiveness of telerehabilitation in the treatment of CVD. The rehabilitation treatments used in the included studies are heterogeneous in terms of program duration, single treatment duration, intensity, and type of exercise. In most of the included studies, in line with previous systematic reviews [8,42,43,44,45], telerehabilitation is able to improve the main outcome measures despite the great variety of the proposed interventions. In the included studies, the treatment designed for the control group is often not described in detail and is rarely supervised by a physiotherapist. On the other hand, when the control group carries out a supervised exercise program, which overlaps with the study group, the results achieved are similar [23,25,35,36] or even lower [32] for the telerehabilitation group.
Most of these studies, however, involve the recruitment of a small sample, like Batalik et al. [23] and Bravo-Escobar et al. [25], so in order to better understand the effects of telerehabilitation, the number of patients recruited should be enlarged, and the exercise programs carried out should be detailed, perhaps even tried to standardize them in relation to pathologies.
However, this contrasts with a study of 850 patients with HF, in which a 9-week full hybrid telerehabilitation program improved pVO2 and QoL but did not increase the percentage of days alive and out of the hospital or reduce mortality and hospitalization over a follow-up period of 14 to 26 months [35]. In the study by Maddison et al. 2015 [32], telerehabilitation was ineffective in improving outcomes. Despite recruiting a sample of 171 participants, this study was based on self-reported outcome measures and also did not include monitoring systems, so the own perceptions of training intensity were likely to be lower than the true physiological intensity required to impact exercise capacity.
In the remaining included studies, however, telerehabilitation proved to be an effective and safe intervention in improving patients’ CRF expressed as pVO2 [26,34], VO2 max [33], or difference in the meters walked at the 6MWT [24,27]; also, these used together with virtual reality is effective in improving anxiety and depression levels [29,30], selective attention, and conflict resolution ability [38] and in reducing risk factors (i.e., waist-to-hip ratio, BMI, ingestion of total fat) [37], with a better cost-effectiveness ratio than center-based cardiac rehabilitation alone [28]. These results are highly encouraging for the implementation of telerehabilitation and telemonitoring systems, especially thanks to the creation of devices that are increasingly easy to use and reliable, which allow rehabilitation to be carried out safely, overcoming geographical and socio-economic gaps. In order to make these technologies more effective and widely used, however, a new approach is needed from both practitioners’ and patients’ sides. This requires extensive digital literacy and the ability to transfer the traditional therapeutic relationship into a new setting that certainly offers promising possibilities for interaction, as demonstrated by the high patient compliance and adherence to telerehabilitation [46,47], which, however, should be further studied and deepened in the various fields of application [48,49,50].
5. Conclusions
With this systematic review, we have shown, overall, that CTR can be an advantageous alternative in improving the functional outcome of patients with CVD, especially due to the technological advances we have been assisting in recent years, which allow real-time monitoring and transmission of vital and movement parameters, offering a care experience comparable to traditional center-based rehabilitation. Moreover, compared to center-based rehabilitation, CTR can offer further advantages, with better cost-effectiveness, the breakdown of geographical barriers, and the improvement of access to treatment for the female population, which is traditionally more socially committed. Furthermore, CTR treatment is safe, can lead to increased levels of participation, and can improve long-term cardiovascular risk management. We also hope that international guidelines will be produced with the aim of reducing the variety of treatment programs and thus improving their effectiveness, and we hope that more studies will be conducted to investigate the long-term benefits of telerehabilitation.
6. Limitation
This systematic review has several limitations, such as small sample size and composition—in fact, many studies had fewer than 100 participants, and most of the patients were males. In addition, socio-demographic data, cultural and economic level, and place of residence are often lacking. However, such information would be necessary to truly understand the effectiveness and safety of telerehabilitation in the treatment of CVD. Additionally, the included studies were limited to papers written in English papers, and original published research articles were only searched for in three databases.
Author Contributions
Conceptualization, M.G., M.C. (Mariaconsiglia Clalabrese), and A.B.; writing—original draft preparation, M.C. (Mariaconsiglia Clalabrese), M.G., A.B., M.R.R., V.V., and C.V.; writing—review and editing, M.C. (Mariaconsiglia Calabrese), M.G., G.G. (Giovanni Granata), and F.C.; supervision, P.B., M.C. (Michele Ciccarelli), A.B., A.C., and G.G. (Gennaro Galasso); linguistic revision of the manuscript, C.I. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
All data generated or analyzed during this study are included in this published article.
Acknowledgments
Ministry of Health Development and Cohesion Plan 2014–2020 Project: “Monitoring and Analysis System based on aRTificial intelligence for patients with chronic CARdiac decompensation with minimally invasive and wearable Evolved medical devices—SMART-CARE” identified by CUP D43C22002120006.
Conflicts of Interest
The authors declare no conflicts of interest.
Appendix A. Search Strategy
Database: PubMed
Date searched: 27 January 2024
Search Strategy:
- #1
- “Cardiovascular Diseases” [Mesh]
- #2
- Cardiovascular Disease OR Disease, Cardiovascular OR Major Adverse Cardiac Events OR Cardiac Events OR Cardiac Event OR Event, Cardiac OR Adverse Cardiac Event OR Adverse Cardiac Events OR Cardiac Event, Adverse OR Cardiac Events, Adverse
- #3
- #1 or #2
- #4
- “Telerehabilitation” [Mesh]
- #5
- Telerehabilitation OR Tele-rehabilitation OR Tele rehabilitation OR Tele-rehabilitations OR Remote Rehabilitation OR Rehabilitation, Remote OR Rehabilitations, Remote OR Remote Rehabilitations OR Virtual Rehabilitation OR Rehabilitation, Virtual OR Rehabilitations, Virtual OR Virtual Rehabilitations
- #6
- #4 or #5
- #7
- #3 and #6
Filters applied: Randomized Controlled Trial, English, from 1 January 2015–27 January 2024
Results: 235
Database: Web Of Science
Date searched: 27 January 2024
Search Strategy:
- #1
- Cardiovascular Disease OR Disease, Cardiovascular OR Major Adverse Cardiac Events OR Cardiac Events OR Cardiac Event OR Event, Cardiac OR Adverse Cardiac Event OR Adverse Cardiac Events OR Cardiac Event, Adverse OR Cardiac Events, Adverse (All Fields)
- #2
- Telerehabilitation OR Tele-rehabilitation OR Tele rehabilitation OR Tele-rehabilitations OR Remote Rehabilitation OR Rehabilitation, Remote OR Rehabilitations, Remote OR Remote Rehabilitations OR Virtual Rehabilitation OR Rehabilitation, Virtual OR Rehabilitations, Virtual OR Virtual Rehabilitations (All Fields)
- #3
- Article (Document Type) AND 2015–2024 (Year Published)
- #4
- #1 AND #2 AND #3
Results: 207
Database: Scopus
Date searched: 27 January 2024
Search Strategy:
- #1
- Cardiovascular Disease OR Disease, Cardiovascular OR Major Adverse Cardiac Events OR Cardiac Events OR Cardiac Event OR Event, Cardiac OR Adverse Cardiac Event OR Adverse Cardiac Events OR Cardiac Event, Adverse OR Cardiac Events, Adverse
- #2
- Telerehabilitation OR Tele-rehabilitation OR Tele rehabilitation OR Tele-rehabilitations OR Remote Rehabilitation OR Rehabilitation, Remote OR Rehabilitations, Remote OR Remote Rehabilitations OR Virtual Rehabilitation OR Rehabilitation, Virtual OR Rehabilitations, Virtual OR Virtual Rehabilitations
- #3
- #1 AND #2
Results: 60
References
- Frederix, I.; Solmi, F.; Piepoli, M.F.; Dendale, P. Cardiac telerehabilitation: A novel cost-efficient care delivery strategy that can induce long-term health benefits. Eur. J. Prev. Cardiol. 2017, 24, 1708–1717. (In English) [Google Scholar] [CrossRef] [Scilit]
- McDonagh, T.A.; Metra, M.; Adamo, M.; Gardner, R.S.; Baumbach, A.; Böhm, M.; Burri, H.; Butler, J.; Čelutkienė, J.; Chioncel, O.; et al. 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur. Heart J. 2021, 42, 3599–3726. (In English) [Google Scholar] [CrossRef] [Scilit]
- Heidenreich, P.A.; Bozkurt, B.; Aguilar, D.; Allen, L.A.; Byun, J.J.; Colvin, M.M.; Deswal, A.; Drazner, M.H.; Dunlay, S.M.; Evers, L.R.; et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation 2022, 145, e895–e1032. (In English) [Google Scholar] [CrossRef] [Scilit]
- Bozkurt, B.; Fonarow, G.C.; Goldberg, L.R.; Guglin, M.; Josephson, R.A.; Forman, D.E.; Lin, G.; Lindenfeld, J.; O’connor, C.; Panjrath, G.; et al. Cardiac Rehabilitation for Patients With Heart Failure: JACC Expert Panel. J. Am. Coll. Cardiol. 2021, 77, 1454–1469. (In English) [Google Scholar] [CrossRef] [Scilit]
- Cowie, A.; Buckley, J.; Doherty, P.; Furze, G.; Hayward, J.; Hinton, S.; Jones, J.; Speck, L.; Dalal, H.; Mills, J. Standards and core components for cardiovascular disease prevention and rehabilitation. Heart 2019, 105, 510–515. (In English) [Google Scholar] [CrossRef] [Scilit]
- Taylor, R.S.; Dalal, H.M.; Zwisler, A.D. Cardiac rehabilitation for heart failure: ‘Cinderella’ or evidence-based pillar of care? Eur. Heart J. 2023, 44, 1511–1518. (In English) [Google Scholar] [CrossRef] [Scilit]
- Cooper, L.B.; Mentz, R.J.; Sun, J.-L.; Schulte, P.J.; Fleg, J.L.; Cooper, L.S.; Piña, I.L.; Leifer, E.S.; Kraus, W.E.; Whellan, D.J.; et al. Psychosocial Factors, Exercise Adherence, and Outcomes in Heart Failure Patients: Insights From Heart Failure: A Controlled Trial Investigating Outcomes of Exercise Training (HF-ACTION). Circ. Heart Fail. 2015, 8, 1044–1051. (In English) [Google Scholar] [CrossRef] [Scilit]
- Zhong, W.; Liu, R.; Cheng, H.; Xu, L.; Wang, L.; He, C.; Wei, Q. Longer-Term Effects of Cardiac Telerehabilitation on Patients With Coronary Artery Disease: Systematic Review and Meta-Analysis. JMIR mHealth uHealth 2023, 11, e46359. (In English) [Google Scholar] [CrossRef] [Scilit]
- Keteyian, S.J.; Jackson, S.L.; Chang, A.; Brawner, C.A.; Wall, H.K.; Forman, D.E.; Sukul, D.; Ritchey, M.D.; Sperling, L.S. Tracking Cardiac Rehabilitation Utilization in Medicare Beneficiaries: 2017 UPDATE. J. Cardiopulm. Rehabil. Prev. 2022, 42, 235–245. (In English) [Google Scholar] [CrossRef] [Scilit]
- Visseren, F.L.J.; Mach, F.; Smulders, Y.M.; Carballo, D.; Koskinas, K.C.; Bäck, M.; Benetos, A.; Biffi, A.; Boavida, J.-M.; Capodanno, D.; et al. 2021 ESC Guidelines on cardiovascular disease prevention in clinical practice. Eur. Heart J. 2021, 42, 3227–3337. (In English) [Google Scholar] [CrossRef] [Scilit]
- Jansen-Kosterink, S.; In ’t Veld, R.H.; Hermens, H.; Vollenbroek-Hutten, M. A Telemedicine Service as Partial Replacement of Face-to-Face Physical Rehabilitation: The Relevance of Use. Telemed. J. E Health 2015, 21, 808–813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peretti, A.; Amenta, F.; Tayebati, S.K.; Nittari, G.; Mahdi, S.S. Telerehabilitation: Review of the State-of-the-Art and Areas of Application. JMIR Rehabil. Assist. Technol. 2017, 4, e7. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cox, N.S.; Corso, S.D.; Hansen, H.; McDonald, C.F.; Hill, C.J.; Zanaboni, P.; A Alison, J.; O'Halloran, P.; Macdonald, H.; Holland, A.E. Telerehabilitation for chronic respiratory disease. Cochrane Database Syst. Rev. 2021, 1, CD013040. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morimoto, Y.; Takahashi, T.; Sawa, R.; Saitoh, M.; Morisawa, T.; Kagiyama, N.; Kasai, T.; Dinesen, B.; Hollingdal, M.; Refsgaard, J.; et al. Web Portals for Patients with Chronic Diseases: Scoping Review of the Functional Features and Theoretical Frameworks of Telerehabilitation Platforms. J. Med. Internet Res. 2022, 24, e27759. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kuroda, Y.; Young, M.; Shoman, H.; Punnoose, A.; Norrish, A.R.; Khanduja, V. Advanced rehabilitation technology in orthopaedics—A narrative review. Int. Orthop. 2021, 45, 1933–1940. (In English) [Google Scholar] [CrossRef] [Scilit]
- Isernia, S.; Pagliari, C.; Morici, N.; Toccafondi, A.; Banfi, P.I.; Rossetto, F.; Borgnis, F.; Tavanelli, M.; Brambilla, L.; Baglio, F. Telerehabilitation Approaches for People with Chronic Heart Failure: A Systematic Review and Meta-Analysis. J. Clin. Med. 2022, 12, 64. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naik, N.; Hameed, B.M.Z.; Sooriyaperakasam, N.; Vinayahalingam, S.; Patil, V.; Smriti, K.; Saxena, J.; Shah, M.; Ibrahim, S.; Singh, A.; et al. Transforming healthcare through a digital revolution: A review of digital healthcare technologies and solutions. Front. Digit. Health 2022, 4, 919985. (In English) [Google Scholar] [CrossRef] [Scilit]
- Chen, C.; Ding, S.; Wang, J. Digital health for aging populations. Nat. Med. 2023, 29, 1623–1630. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palmer, K.; Bowles, K.A.; Lane, R.; Morphet, J. Barriers to Engagement in Chronic Heart Failure Rehabilitation: An Australian Survey. Heart Lung Circ. 2020, 29, e177–e184. (In English) [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. (In English) [Google Scholar] [CrossRef] [Scilit]
- Cumpston, M.S.; McKenzie, J.E.; Welch, V.A.; Brennan, S.E. Strengthening systematic reviews in public health: Guidance in the Cochrane Handbook for Systematic Reviews of Interventions, 2nd edition. J. Public Health 2022, 44, e588–e592. (In English) [Google Scholar] [CrossRef] [Scilit]
- Maher, C.G.; Sherrington, C.; Herbert, R.D.; Moseley, A.M.; Elkins, M. Reliability of the PEDro scale for rating quality of randomized controlled trials. Phys. Ther. 2003, 83, 713–721. (In English) [Google Scholar] [CrossRef] [Scilit]
- Batalik, L.; Dosbaba, F.; Hartman, M.; Batalikova, K.; Spinar, J. Benefits and effectiveness of using a wrist heart rate monitor as a telerehabilitation device in cardiac patients: A randomized controlled trial. Medicine 2020, 99, e19556. (In English) [Google Scholar] [CrossRef] [Scilit]
- Bernocchi, P.; Vitacca, M.; La Rovere, M.T.; Volterrani, M.; Galli, T.; Baratti, D.; Paneroni, M.; Campolongo, G.; Sposato, B.; Scalvini, S. Home-based telerehabilitation in older patients with chronic obstructive pulmonary disease and heart failure: A randomised controlled trial. Age Ageing 2018, 47, 82–88. (In English) [Google Scholar] [CrossRef] [Scilit]
- Bravo-Escobar, R.; González-Represas, A.; Gómez-González, A.M.; Montiel-Trujillo, A.; Aguilar-Jimenez, R.; Carrasco-Ruíz, R.; Salinas-Sánchez, P. Effectiveness and safety of a home-based cardiac rehabilitation programme of mixed surveillance in patients with ischemic heart disease at moderate cardiovascular risk: A randomised, controlled clinical trial. BMC Cardiovasc. Disord. 2017, 17, 66. (In English) [Google Scholar] [CrossRef] [Scilit]
- Cai, C.; Bao, Z.; Wu, N.; Wu, F.; Sun, G.; Yang, G.; Chen, M. A novel model of home-based, patient-tailored and mobile application-guided cardiac telerehabilitation in patients with atrial fibrillation: A randomised controlled trial. Clin. Rehabil. 2022, 36, 40–50. [Google Scholar] [CrossRef] [Scilit]
- Fang, J.; Huang, B.; Xu, D.; Li, J.; Au, W.W. Innovative Application of a Home-Based and Remote Sensing Cardiac Rehabilitation Protocol in Chinese Patients After Percutaneous Coronary Intervention. Telemed. J. E Health 2019, 25, 288–293. (In English) [Google Scholar] [CrossRef] [Scilit]
- Frederix, I.; Hansen, D.; Coninx, K.; Vandervoort, P.; Vandijck, D.; Hens, N.; Van Craenenbroeck, E.; Van Driessche, N.; Dendale, P. Effect of comprehensive cardiac telerehabilitation on one-year cardiovascular rehospitalization rate, medical costs and quality of life: A cost-effectiveness analysis. Eur. J. Prev. Cardiol. 2016, 23, 674–682. (In English) [Google Scholar] [CrossRef] [Scilit]
- Jóźwik, S.; Cieślik, B.; Gajda, R.; Szczepańska-Gieracha, J. Evaluation of the Impact of Virtual Reality-Enhanced Cardiac Rehabilitation on Depressive and Anxiety Symptoms in Patients with Coronary Artery Disease: A Randomised Controlled Trial. J. Clin. Med. 2021, 10, 2148. [Google Scholar] [CrossRef] [Scilit]
- Jóźwik, S.; Cieślik, B.; Gajda, R.; Szczepańska-Gieracha, J. The Use of Virtual Therapy in Cardiac Rehabilitation of Female Patients with Heart Disease. Medicina 2021, 57, 768. [Google Scholar] [CrossRef] [Scilit]
- De Jesus Lima, H.; Da Silva Pinto Souza, R.; Santos e Santos, A.S.M.; Borges, D.L.; Guimaraes, A.R.F.; Ferreira, G.V.D.B.A.; Barros, R.M.; Cordeiro, A.L.L. Virtual reality on pulmonary function and functional independence after coronary artery bypass grafting: Clinical trial. Am. J. Cardiovasc. Dis. 2020, 10, 499–505. [Google Scholar]
- Maddison, R.; Pfaeffli, L.; Whittaker, R.; Stewart, R.; Kerr, A.; Jiang, Y.; Kira, G.; Leung, W.; Dalleck, L.; Carter, K.; et al. A mobile phone intervention increases physical activity in people with cardiovascular disease: Results from the HEART randomized controlled trial. Eur. J. Prev. Cardiol. 2015, 22, 701–709. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maddison, R.; Rawstorn, J.C.; Stewart, R.A.H.; Benatar, J.; Whittaker, R.; Rolleston, A.; Jiang, Y.; Gao, L.; Moodie, M.; Warren, I.; et al. Effects and costs of real-time cardiac telerehabilitation: Randomised controlled non-inferiority trial. Heart 2019, 105, 122–129. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Piotrowicz, E.; Zieliński, T.; Bodalski, R.; Rywik, T.; Dobraszkiewicz-Wasilewska, B.; Sobieszczańska-Małek, M.; Stepnowska, M.; Przybylski, A.; Browarek, A.; Szumowski, Ł.; et al. Home-based telemonitored Nordic walking training is well accepted, safe, effective and has high adherence among heart failure patients, including those with cardiovascular implantable electronic devices: A randomised controlled study. Eur. J. Prev. Cardiol. 2015, 22, 1368–1377. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Piotrowicz, E.; Pencina, M.J.; Opolski, G.; Zareba, W.; Banach, M.; Kowalik, I.; Orzechowski, P.; Szalewska, D.; Pluta, S.; Glówczynska, R.; et al. Effects of a 9-Week Hybrid Comprehensive Telerehabilitation Program on Long-Term Outcomes in Patients with Heart Failure: The Telerehabilitation in Heart Failure Patients (TELEREH-HF) Randomized Clinical Trial. JAMA Cardiol. 2020, 5, 300–308. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Snoek, J.A.; Meindersma, E.P.; Prins, L.F.; Hof, A.W.V.; de Boer, M.-J.; Hopman, M.T.; Eijsvogels, T.M.; de Kluiver, E.P. The sustained effects of extending cardiac rehabilitation with a six-month telemonitoring and telecoaching programme on fitness, quality of life, cardiovascular risk factors and care utilisation in CAD patients: The TeleCaRe study. J. Telemed. Telecare 2021, 27, 473–483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- da Silva Vieira, Á.S.; de Melo, M.C.D.A.; Noites Soares Pinho, A.R.S.; Machado, J.P.; Mendes, J.G.M. The effect of virtual reality on a home-based cardiac rehabilitation program on body composition, lipid profile and eating patterns: A randomized controlled trial. Eur. J. Integr. Med. 2016, 9, 69–78. [Google Scholar] [CrossRef] [Scilit]
- da Silva Vieira, Á.S.; de Melo, M.C.D.A.; Machado, J.P.; Gabriel, J. Virtual reality exercise on a home-based phase III cardiac rehabilitation program, effect on executive function, quality of life and depression, anxiety and stress: A randomized controlled trial. Disabil. Rehabil. Assist. Technol. 2018, 13, 112–123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jingili, N.; Oyelere, S.S.; Nyström, M.B.T.; Anyshchenko, L. A systematic review on the efficacy of virtual reality and gamification interventions for managing anxiety and depression. Front. Digit. Health 2023, 5, 1239435. (In English) [Google Scholar] [CrossRef] [Scilit]
- Dissanayaka, T.; Nakandala, P.; Sanjeewa, C. Physiotherapists’ perceptions and barriers to use of telerehabilitation for exercise management of people with knee osteoarthritis in Sri Lanka. Disabil. Rehabil. Assist. Technol. 2022, 19, 769–778. (In English) [Google Scholar] [CrossRef] [Scilit]
- Lawford, B.J.; Bennell, K.L.; Kasza, J.; Hinman, R.S. Physical Therapists’ Perceptions of Telephone- and Internet Video-Mediated Service Models for Exercise Management of People with Osteoarthritis. Arthritis Care Res. 2018, 70, 398–408. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Antoniou, V.; Davos, C.H.; Kapreli, E.; Batalik, L.; Panagiotakos, D.B.; Pepera, G. Effectiveness of Home-Based Cardiac Rehabilitation, Using Wearable Sensors, as a Multicomponent, Cutting-Edge Intervention: A Systematic Review and Meta-Analysis. J. Clin. Med. 2022, 11, 3772. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anderson, L.; Oldridge, N.; Thompson, D.R.; Zwisler, A.-D.; Rees, K.; Martin, N.; Taylor, R.S. Exercise-Based Cardiac Rehabilitation for Coronary Heart Disease: Cochrane Systematic Review and Meta-Analysis. J. Am. Coll. Cardiol. 2016, 67, 1–12. (In English) [Google Scholar] [CrossRef] [Scilit]
- Ramachandran, H.J.; Jiang, Y.; Tam, W.W.S.; Yeo, T.J.; Wang, W. Effectiveness of home-based cardiac telerehabilitation as an alternative to Phase 2 cardiac rehabilitation of coronary heart disease: A systematic review and meta-analysis. Eur. J. Prev. Cardiol. 2022, 29, 1017–1043. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muñoz-Tomás, M.T.; Burillo-Lafuente, M.; Vicente-Parra, A.; Sanz-Rubio, M.C.; Suarez-Serrano, C.; Marcén-Román, Y.; Franco-Sierra, M.; Muñoz-Tomás, M.T.; Burillo-Lafuente, M.; Vicente-Parra, A.; et al. Telerehabilitation as a Therapeutic Exercise Tool versus Face-to-Face Physiotherapy: A Systematic Review. Int. J. Environ. Res. Public. Health 2023, 20, 4358. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seron, P.; Oliveros, M.-J.; Gutierrez-Arias, R.; Fuentes-Aspe, R.; Torres-Castro, R.C.; Merino-Osorio, C.; Nahuelhual, P.; Inostroza, J.; Jalil, Y.; Solano, R.; et al. Effectiveness of Telerehabilitation in Physical Therapy: A Rapid Overview. Phys. Ther. 2021, 101, pzab053. (In English) [Google Scholar] [CrossRef] [Scilit]
- Kairy, D.; Lehoux, P.; Vincent, C.; Visintin, M. A systematic review of clinical outcomes, clinical process, healthcare utilization and costs associated with telerehabilitation. Disabil. Rehabil. 2009, 31, 427–447. (In English) [Google Scholar] [CrossRef] [Scilit]
- Amin, J.; Ahmad, B.; Amin, S.; Siddiqui, A.A.; Alam, M.K. Rehabilitation Professional and Patient Satisfaction with Telerehabilitation of Musculoskeletal Disorders: A Systematic Review. Biomed. Res. Int. 2022, 2022, 7366063. (In English) [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stamou, M.; Nikolaou, C.; Chοiras, S. Telerehabilitation in Physiotherapy Science: A Scoping Review. Cureus 2024, 16, e54396. (In English) [Google Scholar] [CrossRef] [Scilit]
- Brouwers, R.W.M.; van Exel, H.J.; van Hal, J.M.C.; Jorstad, H.T.; de Kluiver, E.P.; Kraaijenhagen, R.A.; Kuijpers, P.M.J.C.; van der Linde, M.R.; Spee, R.F.; Sunamura, M.; et al. Cardiac telerehabilitation as an alternative to centre-based cardiac rehabilitation. Neth. Heart J. 2020, 28, 443–451. (In English) [Google Scholar] [CrossRef] [Scilit]




Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).