


Abstract
Introduction: This network meta-analysis aimed to assess the efficacy of acupuncture, intravenous lidocaine, and diet compared with other comparators such as physiotherapy and sham/placebo in fibromyalgia patients. Materials and Methods: We searched Embase, PubMed, Scopus, and Web of Science for relevant studies till September 2021. The included studies were randomized controlled clinical trials. For the network meta-analysis, we used the R software. Results: There were 23 included RCTs. The total sample size was 1409 patients. Compared with the sham/placebo group, the network analysis showed the highest improvement in the quality of life in the acupuncture group standardized mean difference (SMD) = −10.28, 95%-CI [−14.96; −5.59]), and then in the physiotherapy group (SMD = −7.48, 95%-CI [−14.72; −0.23]). For the pain, there was a significant reduction with acupuncture (SMD = −1.69, 95%-CI [−2.48; −0.89]), compared with sham/placebo. Regarding depression, it showed a significant reduction with acupuncture (SMD = −9.64, 95%-CI [−16.13; −3.14]) compared with sham/placebo. Finally, for stiffness, it showed no significant differences in the stiffness between acupuncture (SMD = −8.52, 95%-CI [−20.40; 3.36]), fluoxetine (SMD = −6.52, 95%-CI [−29.65; 16.61]), and physiotherapy (SMD = −4.64, 95%-CI [−22.83; 13.54]) compared with sham/placebo. Conclusions: The acupuncture showed a significant effect in the management of fibromyalgia patients. It reduced pain, depression, and enhanced the quality of life. While physiotherapy showed a significant improvement in the quality of life only. In contrast, intravenous lidocaine and diet showed no significant differences when compared with sham/placebo.
1. Introduction
Fibromyalgia (FM) is a condition known for its chronic widespread musculoskeletal pain. It is diagnosed by the American College of Rheumatology (ACR) criteria 2016 [1]. Fibromyalgia patients are usually characterized by moderate-to-severe symptoms including widespread pain, point tenderness, cognitive disturbance, sleep disturbance, psychiatric, and multiple somatic symptoms [1,2,3]. The balance impairments and functionality can considerably influence the FM patients’ quality of life (QoL) [4,5,6]. So, FM patients have difficulties in their daily activities’ performance, and their ability to work [7,8,9,10].
One of the recommended management options for FM includes acupuncture [11]. The reviews offer positive evidence for its efficacy in the improvement of pain and stiffness compared with conventional treatment, or no treatment or drug therapy [12,13]. However, there is no support for its use for physical function disabilities. Acupuncture’s benefits in balance impairment were observed in patients with conditions other than FM [14,15].
FM patients are often treatment-resistant or suffer from unbearable side effects using conventional oral medications. Intravenous (IV) lidocaine is a treatment having peripheral and central-mediated analgesic, anti-inflammatory, as well as antihyperalgesic effects [16,17]. IV lidocaine has been reported to be safe and effective in producing clinically efficient analgesia in patients suffering from various pain disorders [18].
In addition to this, the role of diet has also been investigated as a treatment for FM, as there have been various linked deficiencies to FM. However, in spite of the encouraging results, this cannot be solid evidence, as much of the available regarding this topic had poor quality, different study designs, inadequate sample sizes, and absence of control groups [19].
A recent study suggested that FM was significantly associated with higher risks for suicidal ideations, suicide attempts, and death by suicide in comparison with the general population [20]. So, it is crucial to investigate the treatment options for FM patients, whether physically or psychologically related. There is a significant gap in the literature among FM patients treated with acupuncture, lidocaine, and diet. Some studies reported that these interventions were effective, while others reported they were non-effective.
Therefore, the objective of this study was to conduct a network meta-analysis to compare acupuncture, lidocaine, and diet with other comparators such as physiotherapy and sham/placebo in FM patients.
2. Materials and Methods
2.1. Study Design
This is a systematic review and network meta-analysis, which was performed strictly according to the preferred reporting items of PRISMA guidelines [21,22]. The network meta-analysis is a type of meta-analysis that compares multiple treatments (three or more) by employing direct comparisons of interventions within randomized controlled trials (RCTs) as well as indirect comparisons across trials based on a common comparator. The direct and indirect evidence can be combined as a weighted average, and made comparisons between each arm included.
2.2. Literature Search
A systematic search was conducted on Embase, PubMed, Scopus, and Web of Science, till September 2021. We gathered the search terms from MeSH and common search terms used in the related publications. The keywords included Fibromyalgia, Fibromyalgias, Fibromyalgia–Fibromyositis, Muscular Rheumatism, Fibrositis, Fibrositides, Diffuse Myofascial Pain Syndrome, Fibromyositis–Fibromyalgia Syndrome, Fibromyositis Fibromyalgia Syndrome, Lignocaine, Octocaine, Xylesthesin, Xylocaine, Xylocitin, Dalcaine, Diet, Dietary, Acupuncture, Acupanctom, Pharmacoacupuncture, Acupotomy, and Acupotomies. The full-search strategy is presented in Appendix A.
2.3. Eligibility Criteria and Study Selection
We included RCTs comparing acupuncture, diet, and lidocaine with other comparators such as physiotherapy and sham/placebo in fibromyalgia patients. All studies included were compared with each other by direct or indirect comparisons. We excluded abstracts, non-English studies, articles other than RCTs, and studies without an outcome of interest or used different scales. To exclude the duplicates, we used Endnote software. Two authors initially screened the title and abstract; then, the other two authors screened the relevant full texts and did a manual screening to ensure all suitable articles were included.
2.4. Data Extraction
Three authors extracted data related to the following: (1) Summary and baseline: Study ID, Country, Design, Diagnostic criteria, Study duration (month), Interventions, Sample size, Age, female, Weight, BMI, Years of diagnosis, Fibromyalgia Impact Questionnaire (FIQ), BDI, VAS (mm, mean, SD), Fibromyalgia Severity Scale, and the number of tender points (TPN); (2) The study outcomes: the primary outcome was changed in the QoL, and the secondary outcomes included changes in pain, depression, and stiffness.
2.5. Outcomes’ Scales
The scales used for the QoL were the Fibromyalgia Impact Questionnaire (FIQ) [23], and Short Form-36 [24]. For the pain, the used scales were Numeric Rating Scale (NRS) [25], Visual Analogue Scale (VAS) [25], Chronic Pain Grade Scale [25], widespread pain index (WPI) [26], Short Form of the McGill Pain Questionnaire (SF MPQ) [25], and FIQ (pain) [27]. For the depression scales, there were VAS [25], Beck Depression Inventory (BDI) [28], FIQ (depression) [27], Center for Epidemiologic Studies Depression Scale (CES-D) [29], and Hamilton Depression Rating hetero-evaluation Scale (HDRS) [30]. Finally, regarding the stiffness, the used scales were VAS [25], and FIQ (stiffness) [27].
2.6. Risk of Bias
We used the Cochrane risk of bias tool for RCTs [31]. The domains include random sequence generation, allocation concealment, blinding of participants and personnel, blinding of outcome assessment, incomplete outcome data, selective reporting, and other bias. The assessment consists of low, high, or unclear risk of bias. Two authors assessed the risk of bias in all studies, and the supervisor solved any disagreements.
2.7. Data Synthesis
All analyses were conducted in R software using the net meta package. Data were pooled as standardized mean difference (SMD) (as the outcomes were assessed by different scales) and 95% CI. Data were considered significant if p < 0.05. We measured heterogeneity using the I-square test and Chi-Square test. Significant heterogeneity was considered if Chi-Square p < 0.1. When heterogeneity was found, we used the random-effect model and tried to solve the heterogeneity by sensitivity analysis using the leave-one-out method. The publication bias was assessed in the outcomes reported in more than 10 studies.
3. Results
3.1. Literature Search
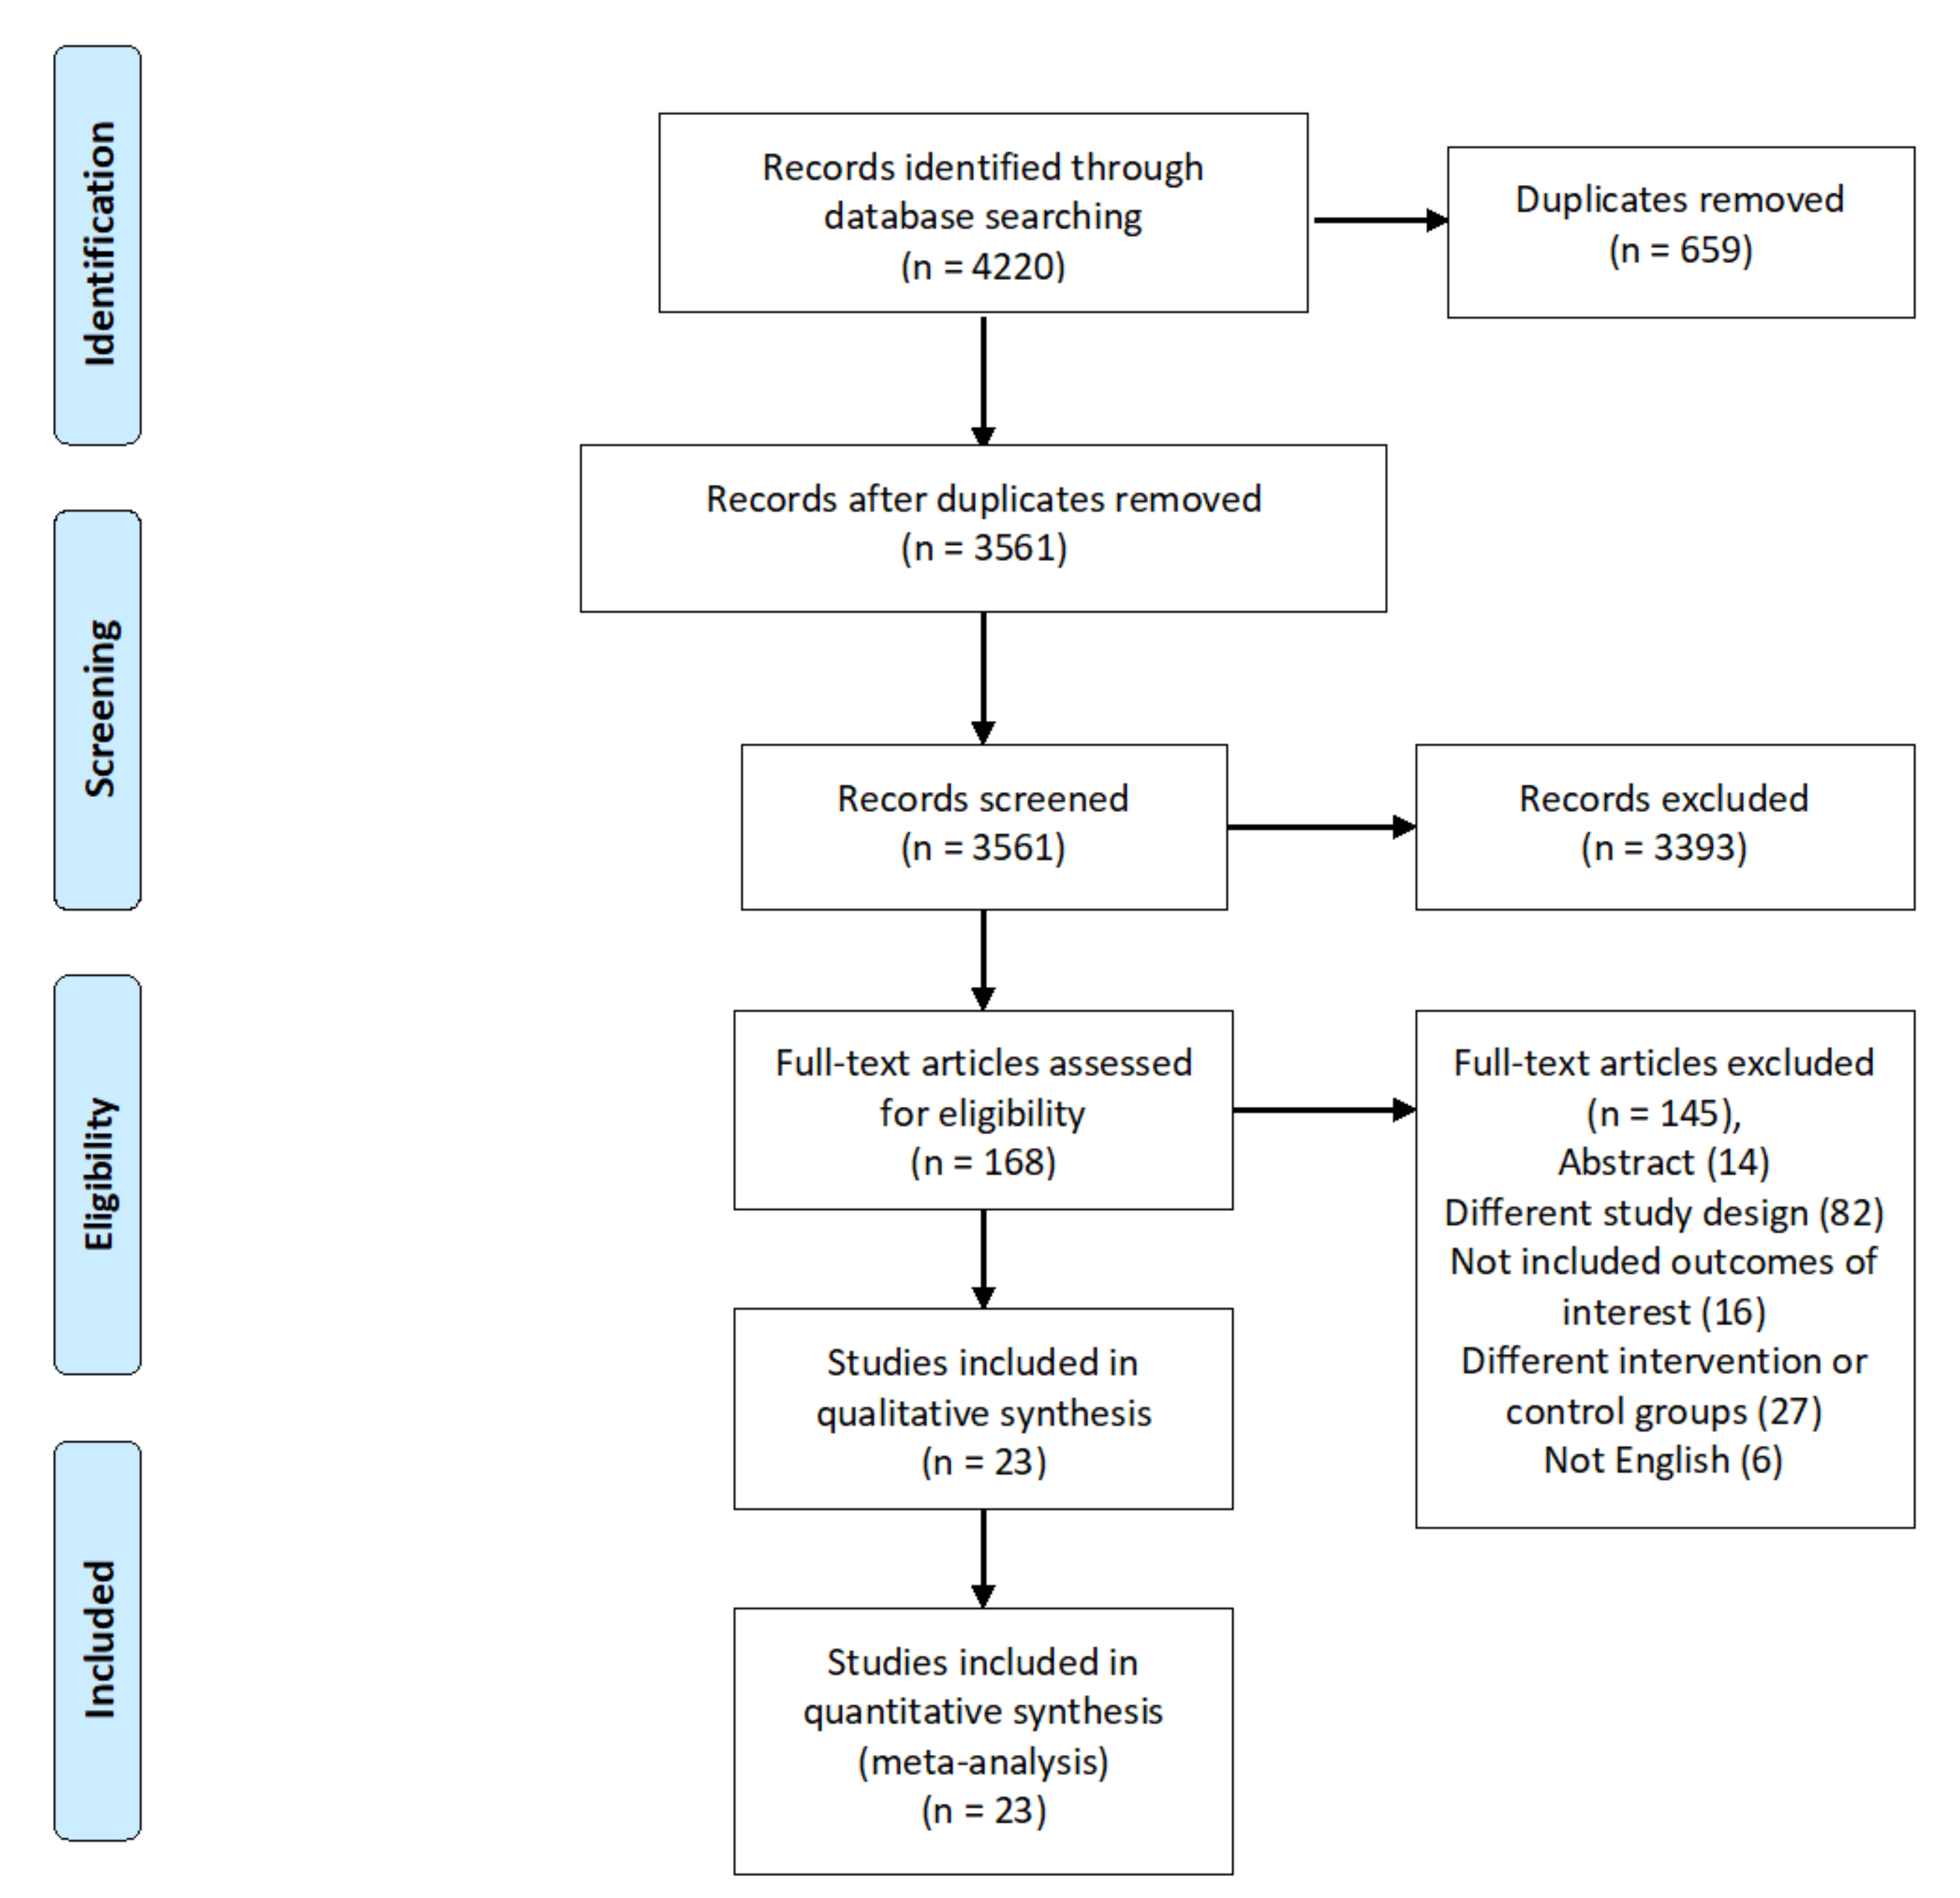
The initially identified records were 4220 in number. Following duplicates’ removal, the remaining records (3561) were screened. Out of them, 168 went through full-text screening. Finally, there were 23 included studies in the analysis [32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48]. Figure 1 PRISMA included the studies’ summary and population’s baseline characters.
Figure 1.
The figure shows the PRISMA flow diagram.
All the studies were RCTs. The countries included Spain, Brazil, the USA, Turkey, and others. The interventions included acupuncture, lidocaine, fluoxetine, physiotherapy, nutraceutical, (Inflammatory Gut–Brain Axis Control) (IGUBAC)-Diet, weight reduction, olive tree-based food supplement, transcutaneous electrical nerve stimulation (TENS), cupping, and sham/placebo. The total sample size was 1409 patients. The majority of the included patients were females, see Table 1.
Table 1.
Summary and baseline characteristics of the included studies.
3.2. Risk of Bias
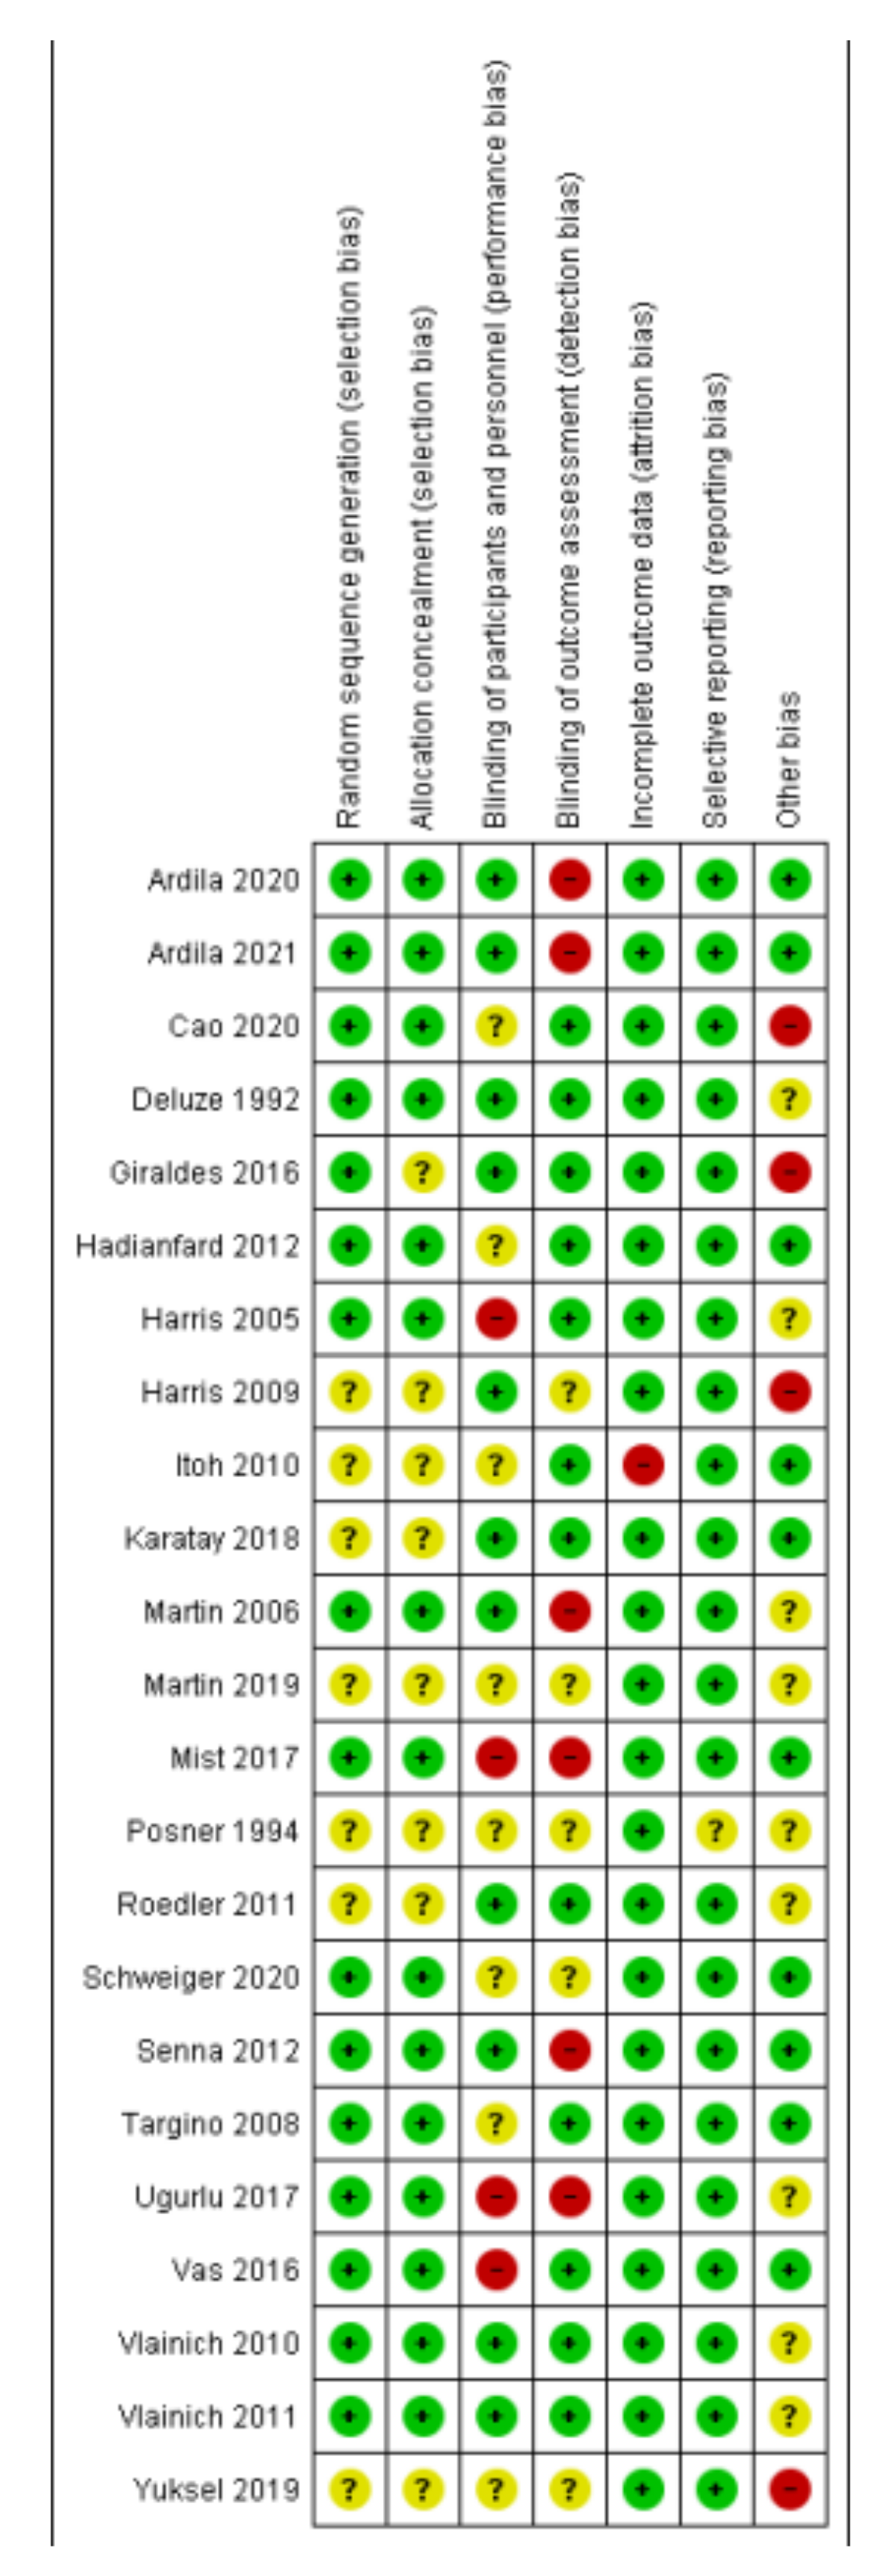
Most of the included studies had an overall low or moderate risk of bias. However, four of them had a risk of bias as regards the blinding of participants and personnel. In addition, six of them had a high risk of bias regarding the blinding of the outcome assessment. Posner et al. showed an unclear risk of bias for all domains except for the incomplete outcome data, which had a low risk of bias. Other details are provided in Figure 2.
Figure 2.
Risk of bias summary.
3.3. Outcomes
3.3.1. Quality of Life (QoL)
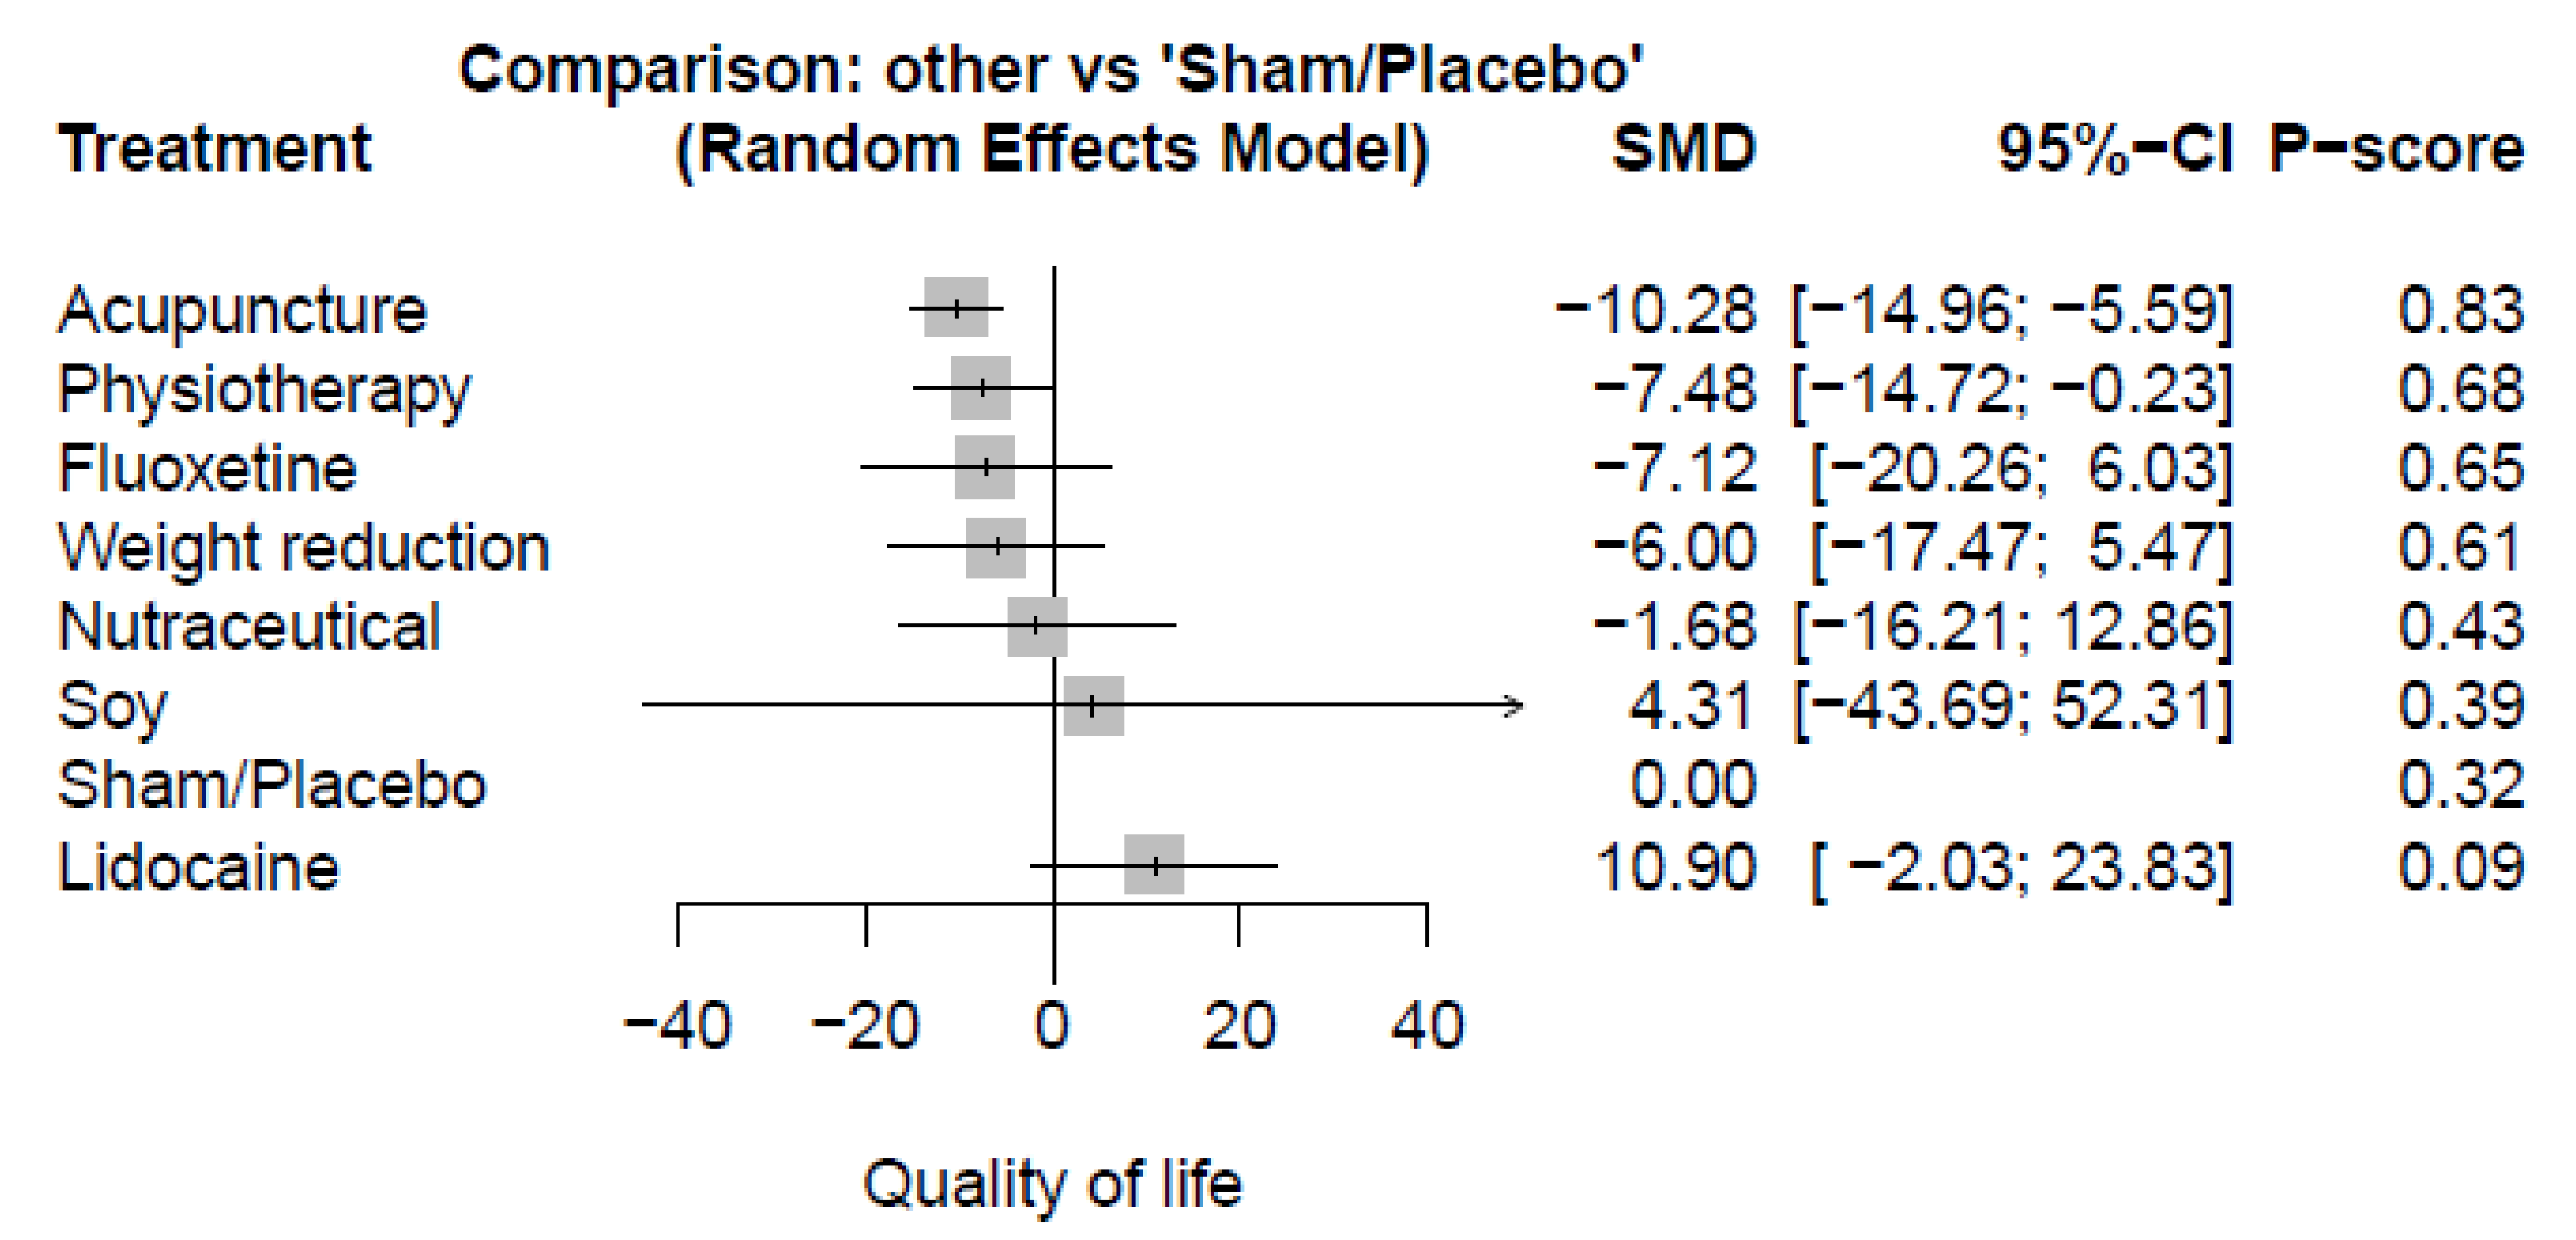
Twelve studies reported the QoL outcome. The pooled estimate of the QoL change from baseline to end-point showed the highest significant improvement in acupuncture (SMD = −10.28, 95%-CI [−14.96; −5.59]) compared with sham/placebo. In addition, the physiotherapy group showed a significant improvement (SMD = −7.48, 95%-CI [−14.72; −0.23]). On the other hand, there were no significant variations between fluoxetine (SMD = −7.12, 95%-CI [−20.26; 6.03]), weight reduction (SMD = −6.00, 95%-CI [−17.47; 5.47]), nutraceutical (SMD = −1.68, 95%-CI [−16.21; 12.86]), soy (SMD = 4.31, 95%-CI [−43.69; 52.31]), and lidocaine (SMD = 10.90, 95%-CI [−2.03; 23.83]) compared with sham/placebo. (Figure 3 and Figure S1) Acupuncture and physiotherapy showed significant variation compared with lidocaine (SMD = −21.18, 95%-CI [−34.92; −7.43], and (SMD = −18.38, 95%-CI [−33.20; −3.56]), respectively. (See Table S1 in the Supplementary File S1 for details).
Figure 3.
Plot of Quality of life (QoL); SMD: standardized mean difference, CI: confidence interval.
3.3.2. Pain
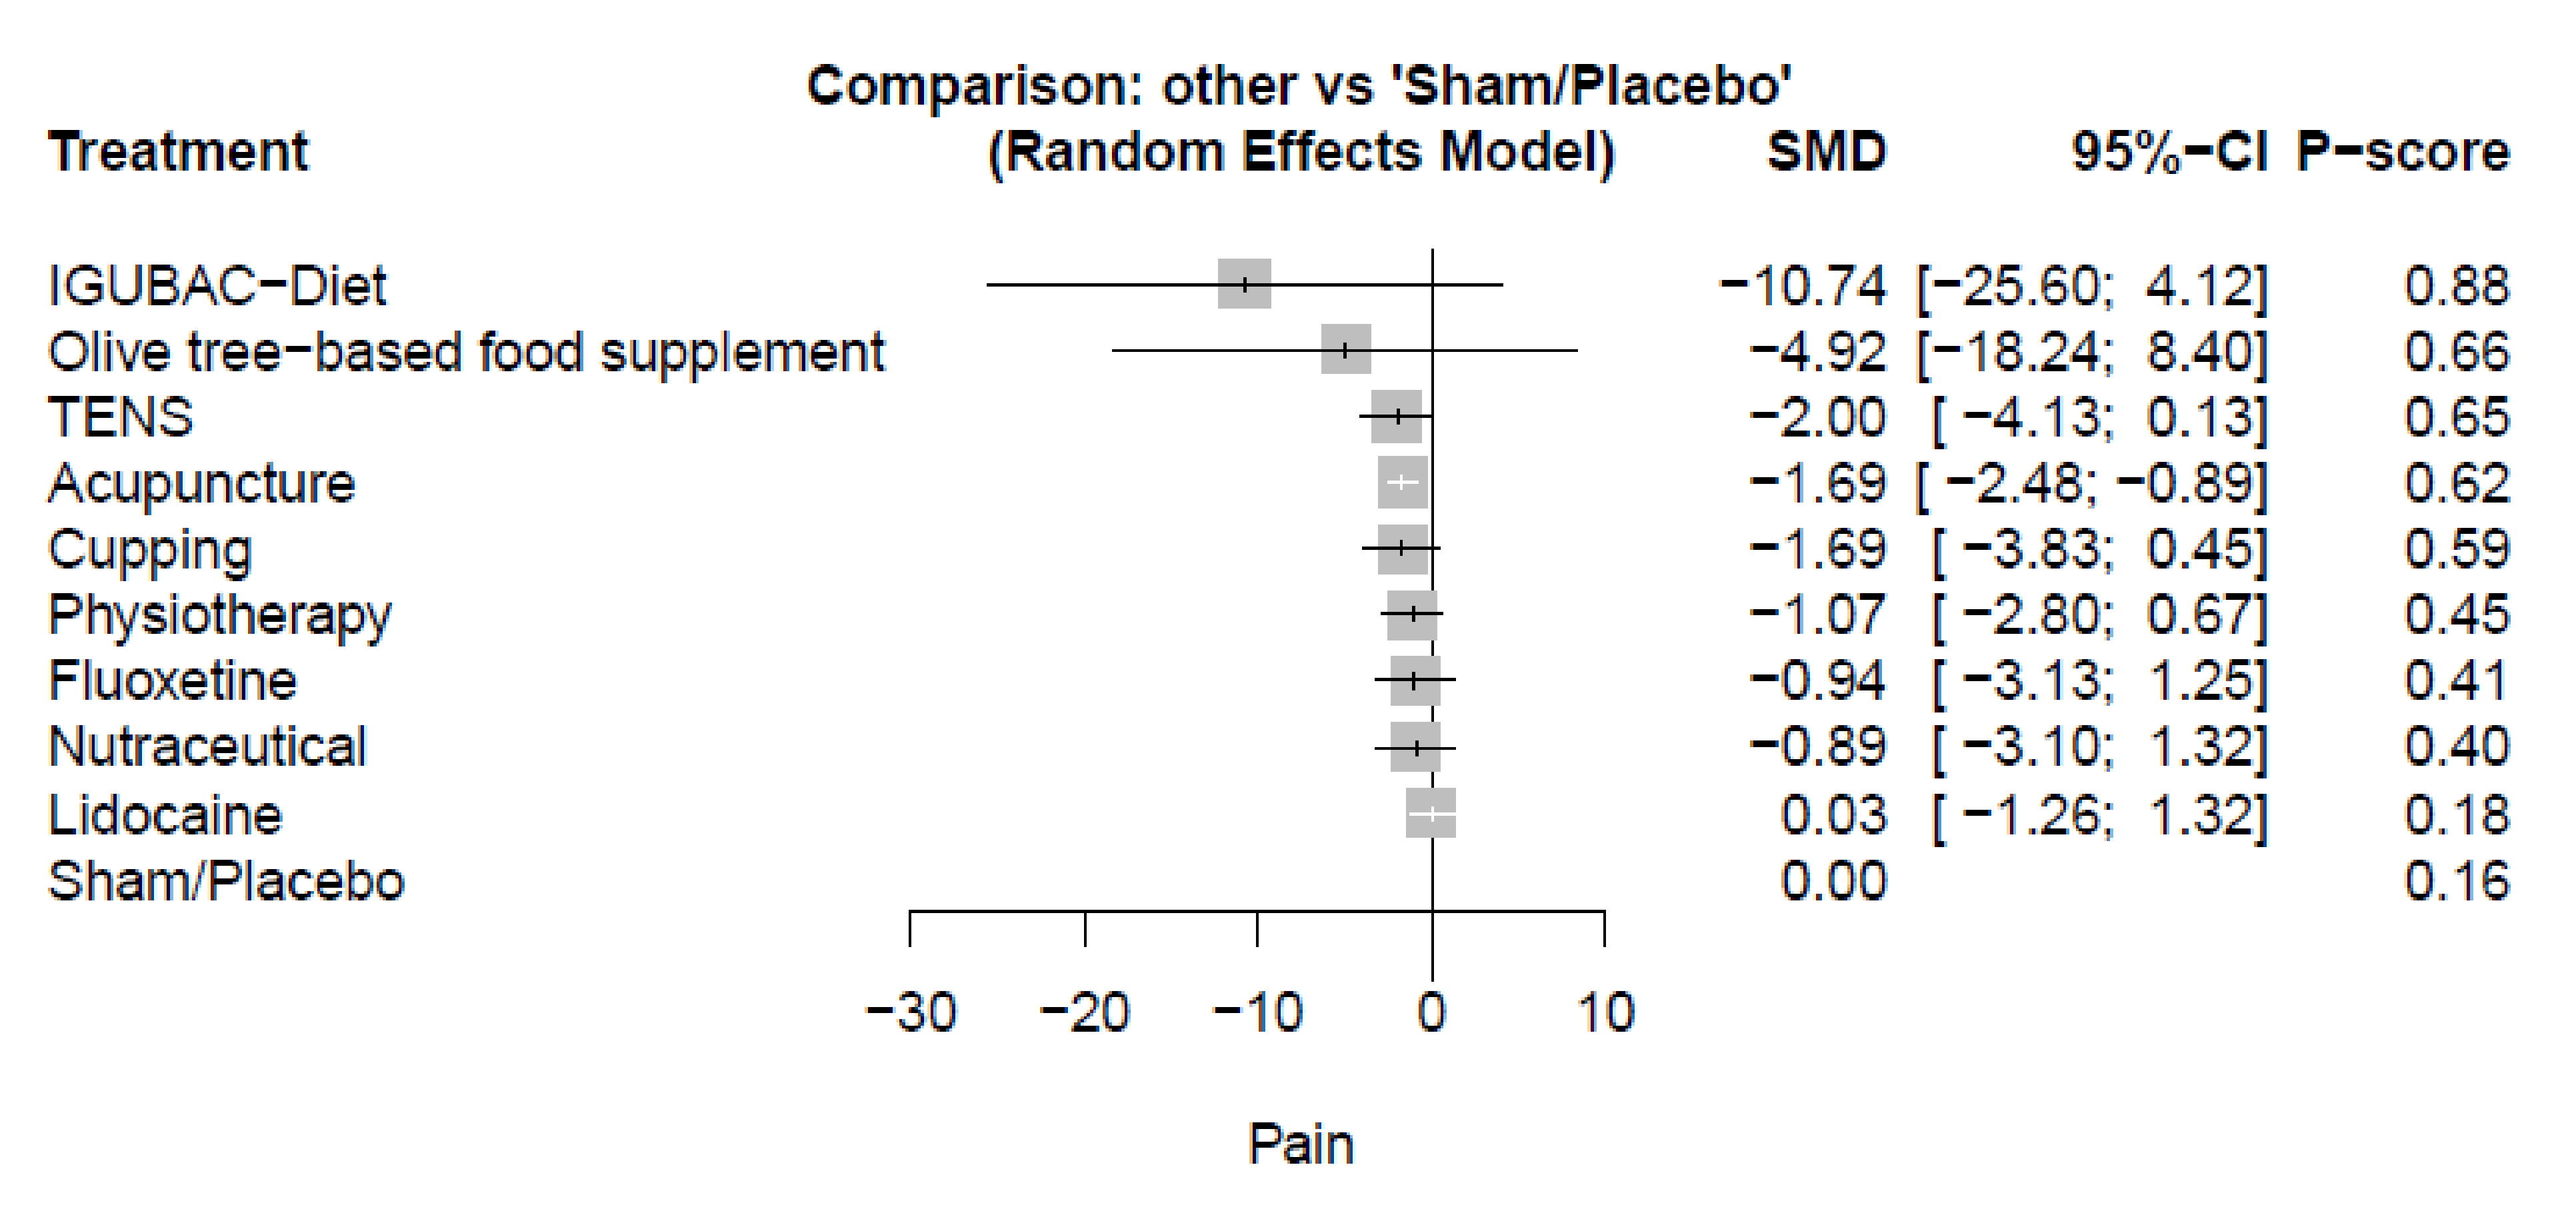
Seventeen studies reported the pain outcome. The pooled estimate of pain change from baseline to end-point showed a significant decrease with acupuncture compared with sham/placebo (SMD = −1.69, 95%-CI [−2.48; −0.89]). There were no other significant differences in IGUBAC−Diet (SMD = -10.74, 95%-CI [−25.60; 4.12]), olive tree-based food supplement (SMD = −4.92, 95%-CI [−18.24; 8.40]), TENS (SMD = −2.00, 95%-CI [−4.13; 0.13]), cupping (SMD = −1.69, 95%-CI [−3.83; 0.45]), physiotherapy (SMD = −1.07, 95%-CI [−2.80; 0.67]), fluoxetine (SMD = −0.94, 95%-CI [−3.13; 1.25]), nutraceutical (SMD = −0.89, 95%-CI [−3.10; 1.32]), and lidocaine (SMD = 0.03, 95%-CI [−1.26; 1.32]) compared with sham/placebo. (Figure 4 and Figure S2) Other significant variations were found in acupuncture compared with lidocaine (SMD = −1.72, 95% [−3.23; −0.20]). There were no other significant differences between any measured comparators. (See Table S2 in the Supplementary File S1 for details).
Figure 4.
Plot of pain; SMD: standardized mean difference, CI: confidence interval.
3.3.3. Depression
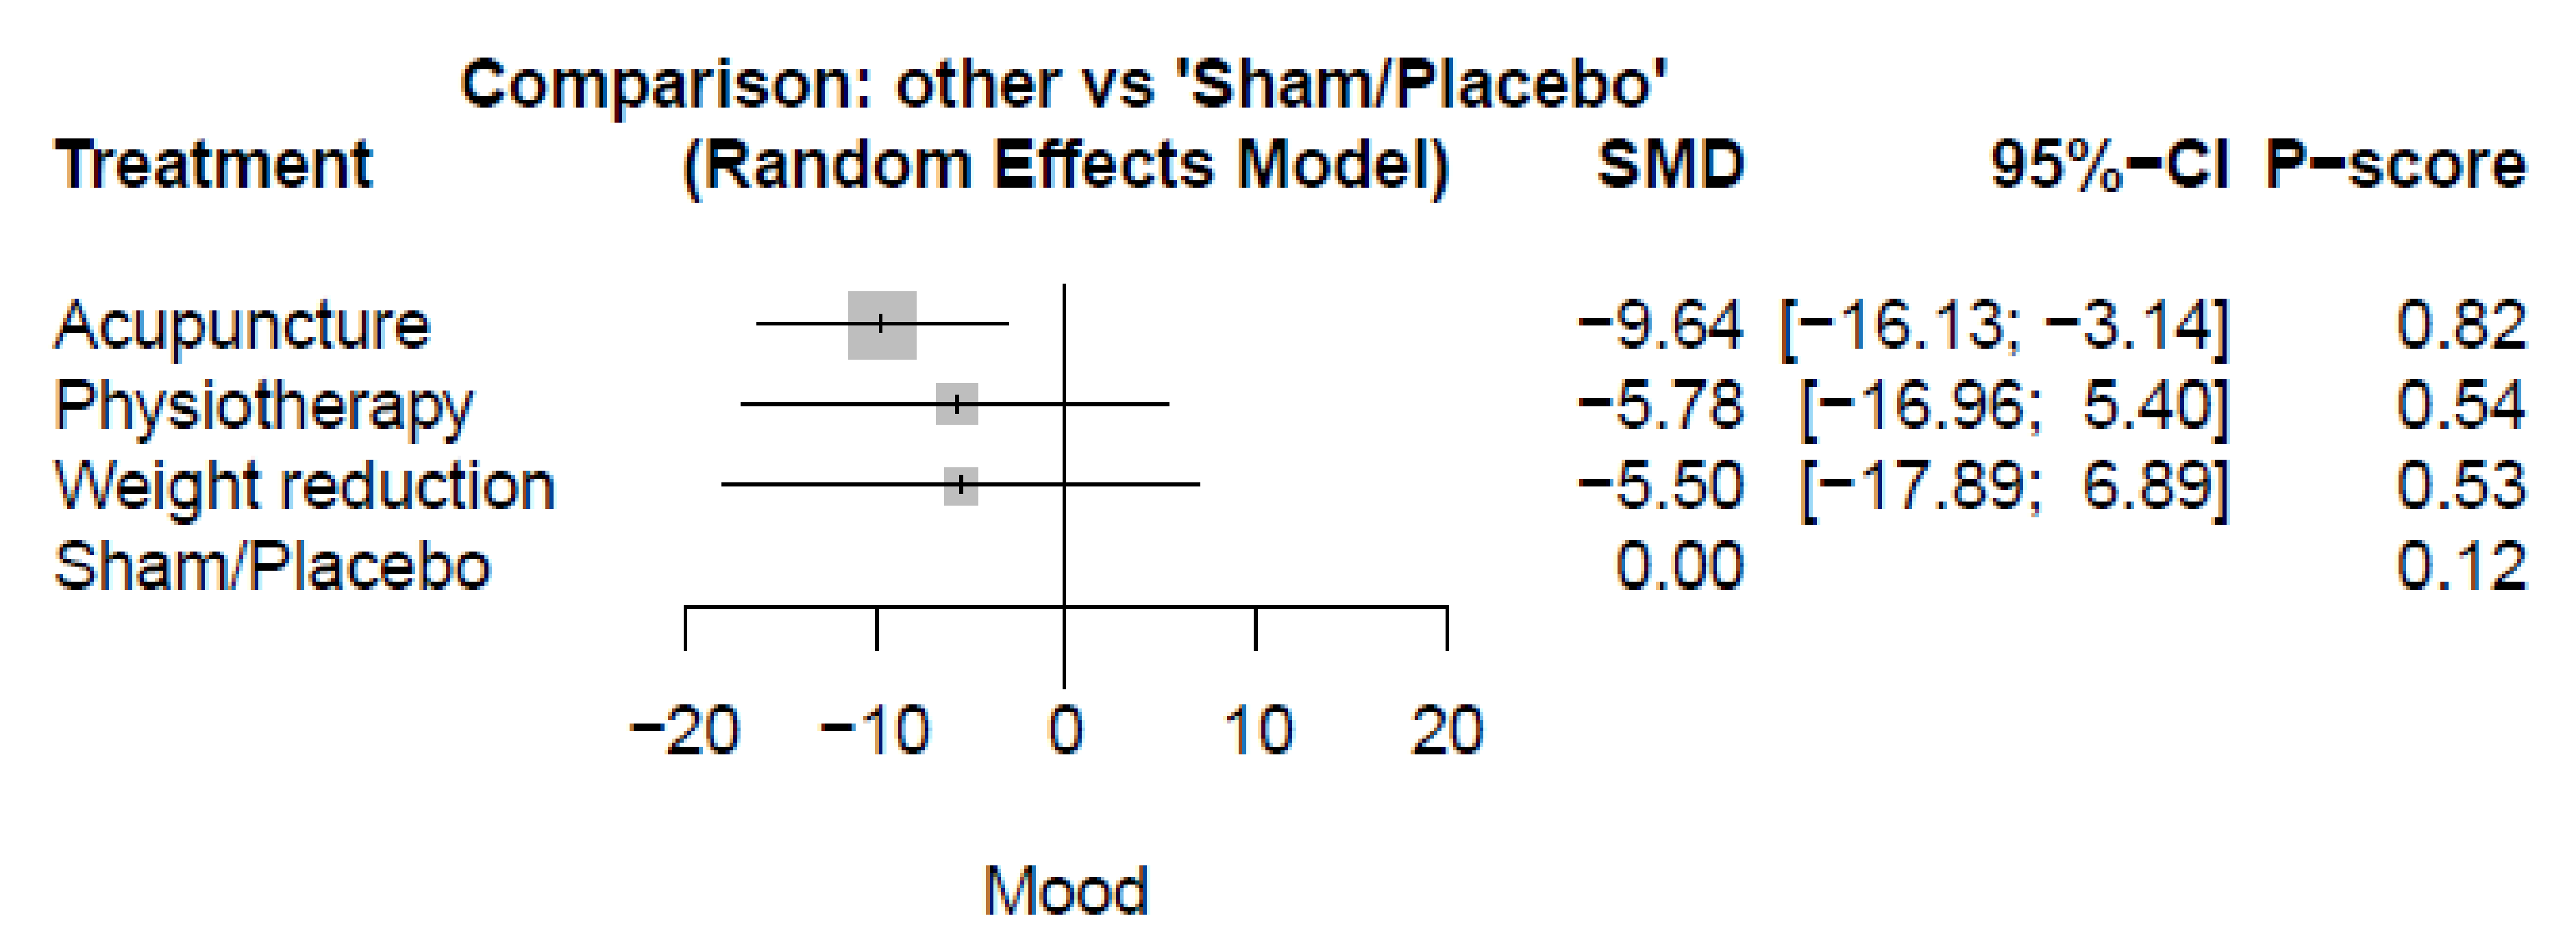
Seven studies reported the depression outcome. The acupuncture showed the highest significant reduction in depression (SMD = −9.64, 95%-CI [−16.13; −3.14]) compared with sham/placebo. However, there were no significant differences in physiotherapy (SMD = −5.78, 95%-CI [−16.96; 5.40]), or weight reduction (SMD = −5.50, 95%-CI [−17.89; 6.89]) compared with sham/placebo. (Figure 5 and Figure S3) In addition, there were no other significant differences between the various comparators. (See Table S3 in the Supplementary File S1 for details).
Figure 5.
Plot of depression; SMD: standardized mean difference, CI: confidence interval.
3.3.4. Stiffness
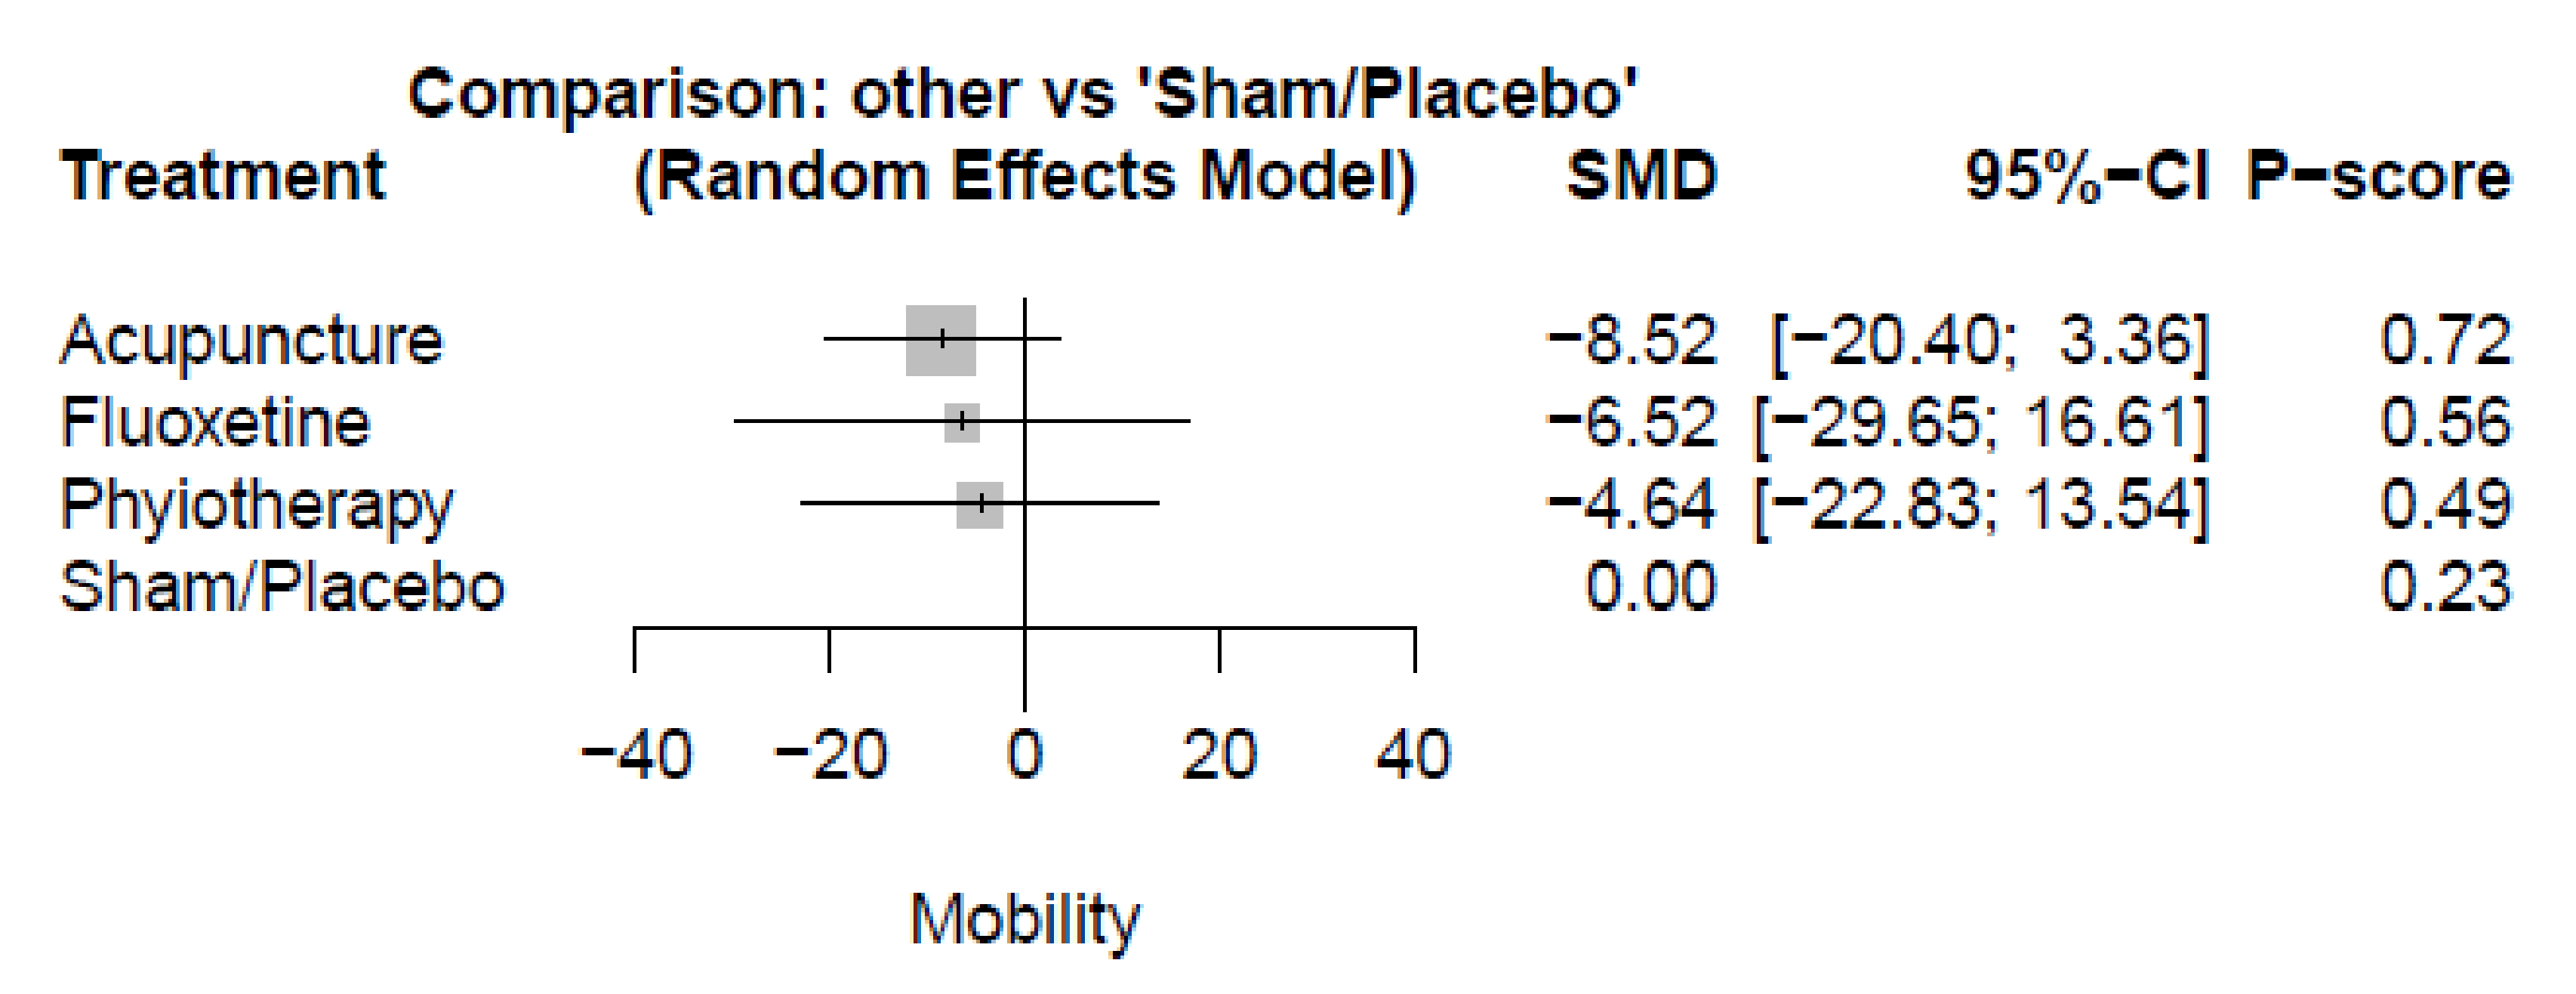
Four studies assessed the stiffness outcome. The pooled estimate of stiffness change from baseline to end-point showed non-significant differences between acupuncture (SMD = −8.52, 95%-CI [−20.40; 3.36]), fluoxetine (SMD = −6.52, 95%-CI [−29.65; 16.61]), and physiotherapy (SMD = −4.64, 95%-CI [−22.83; 13.54]) compared with sham/placebo. (Figure 6 and Figure S4) There were no other significant differences between the various comparators. (See Table S4 in the Supplementary File S1 for details).
Figure 6.
Plot of stiffness; SMD: standardized mean difference, CI: confidence interval.
3.4. Heterogeneity
All outcomes assessed under random effect model and the results were heterogeneous (p < 0.0001, I2 = 95.3–99.4%). The heterogeneity could not be solved by the leave-one-out method.
3.5. Publication Bias
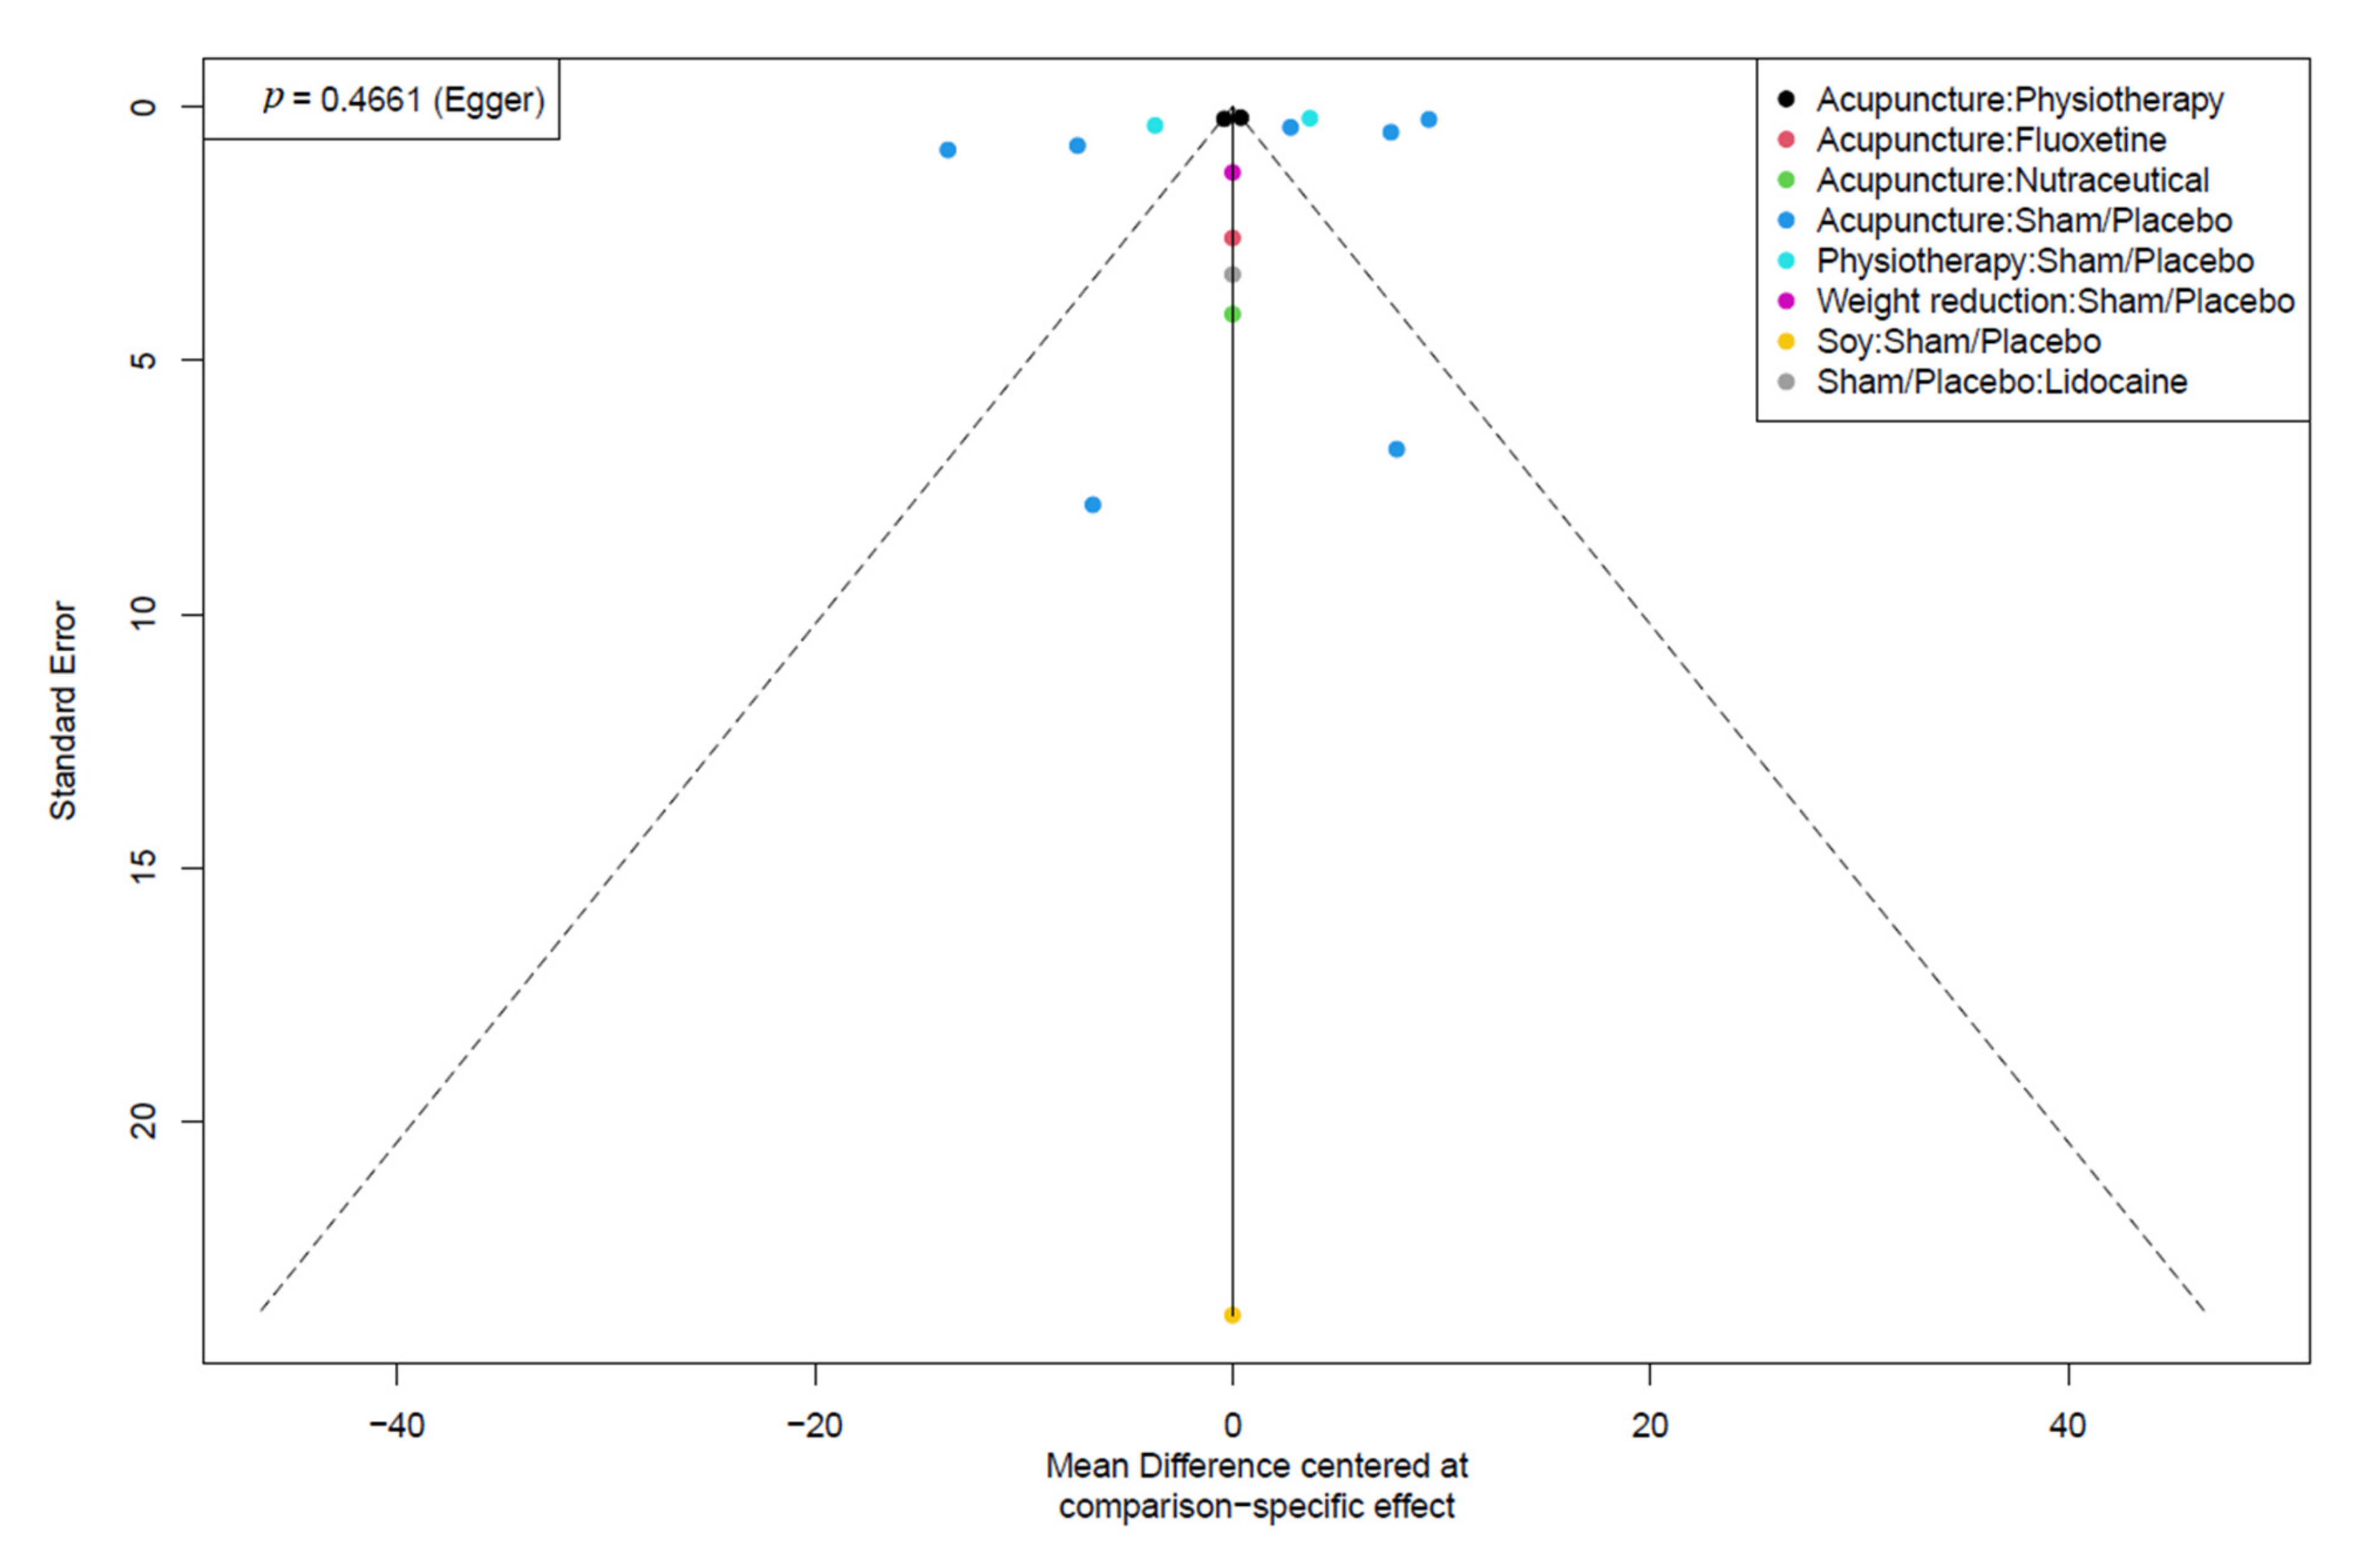
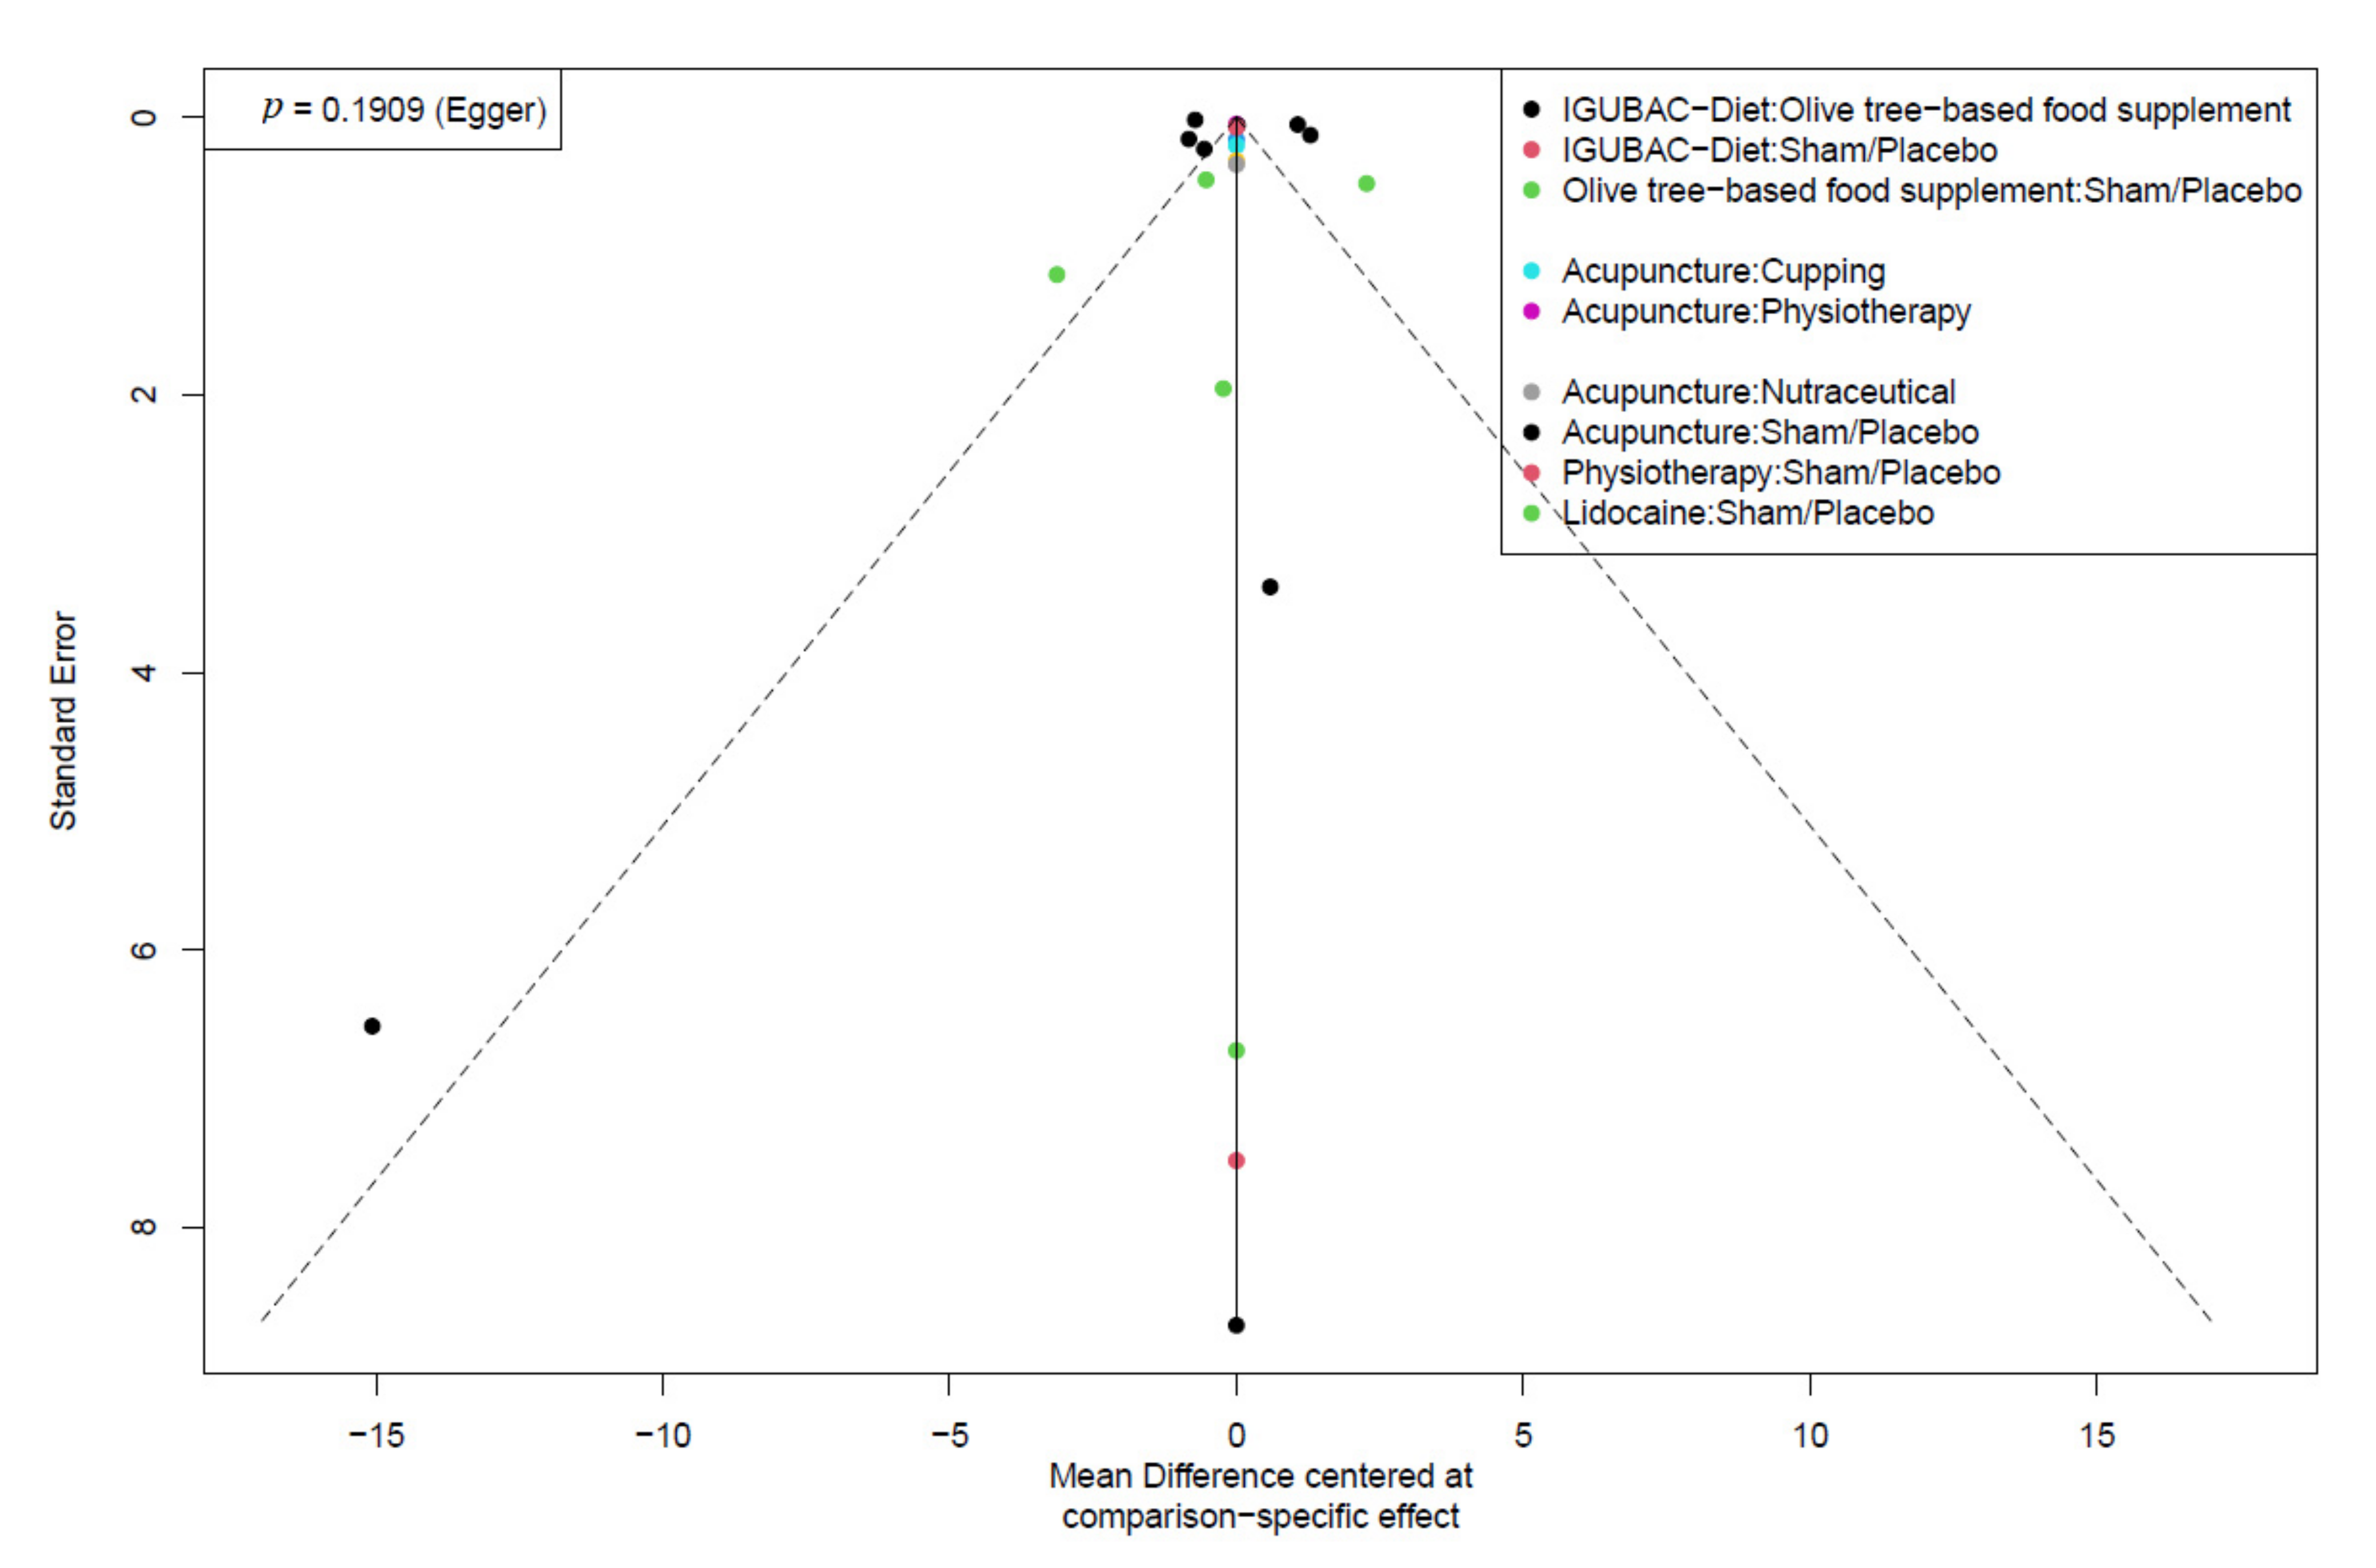
According to Egger et. al., we could not assess the publication bias of the stiffness and depression outcomes because the analyses included less than ten studies. We noticed no publication bias in the QoL and pain outcomes by visual inspection of the funnel plot and p-value of Egger’s test. Figure 7 and Figure 8 showed the funnel plots of the QoL and pain outcomes, respectively.
Figure 7.
Funnel plot of the QoL outcome.
Figure 8.
Funnel plot of the pain outcome.
4. Discussion
The results showed a significant improvement in the QoL with acupuncture and physiotherapy, and the other comparators showed no significant differences. As regards the pain, the study showed a significant decrease in the acupuncture group only. Regarding depression, there was a significant reduction with acupuncture. On the other hand, there were no significant variations with physiotherapy, or weight reduction. Finally, regarding the stiffness, the results showed no significant differences between acupuncture, fluoxetine, and physiotherapy compared with sham/placebo.
Mayhew and Ernst previously did not recommend acupuncture for FM in their meta-analysis of RCTs [49]. Other reviews also had similar negative conclusions and results to them [13,50,51]. Furthermore, a Cochrane review of 9 studies with 395 patients showed large differences in results. Three showed small, short-lasting effects (all electro-acupuncture), and six did not differ from sham acupuncture [12]. All these reviews included a small number of studies with a small sample size, which may affect the results. In addition, the editorial by Colquhoun and Novella reported that acupuncture is ineffective, and the trials’ positive results are probably false-positive results due to multiple reasons, including bias and low prior probability [52]. On the other hand, the most recent meta-analysis of them concluded that acupuncture was both effective and safe as a treatment for FM patients and recommended its use for FM management [53]. Similar to our study, they also showed pain reduction, and an improvement in the QoL. The analgesic effects of acupuncture activate both the peripheral and central pain control systems through the release of different endogenous opioids or nonopioid compounds, for example, beta-endorphins, enkephalins, dynorphins, serotonin, norepinephrine, and others [54,55,56].
In FM patients, nutritional therapy may be controversial, yet promising. Improvements in pain and functional repercussion in FM patients appeared to occur with a hypo-caloric diet, a raw vegetarian diet, or a diet low in fermentable oligo-, di-, monosaccharides, and polyols, in addition to the QoL and sleep, anxiety and depression, and inflammatory biomarkers. However, those data had several limitations [57]. Various other studies showed promising but limited data about the role of diet in FM patients [58,59]. Our study showed contrary results, as the diet did not show significant differences.
In a previous pilot study, lidocaine showed improvements in the VAS pain scale in FM patients, suggesting that periodic IV infusion of lidocaine might offer extra benefits for FM patients receiving conventional treatment [41]. On the other hand, later on, other studies showed that lidocaine had no improvements when added to amitriptyline [34,60]. Similar to them, our study showed no significant improvements with lidocaine. Giraldes et al. suggested that the absence of difference in the analgesic effect might have been because amitriptyline alone had a sufficient effect. They also suggested that lidocaine required to be administered at smaller intervals to gain a difference in effect [60].
Our inclusion of RCTs only, and the moderate to high quality of the included studies added more validity to our data. Even though our study included various studies, those studies mainly included a small sample size, which limits our data. Another limitation in our study is the different ways of diagnosing fibromyalgia patients in each included study, even when using the ACR criteria. Furthermore, most of the included studies were mainly about acupuncture, and they had different types, points, and numbers of acupuncture. Another limitation includes that some studies had different time points.
Therefore, we recommend future research focus on assessing the effect of diet and lidocaine on FM patients. We also recommend future research have similar time points and use a specific scale for each outcome.
5. Conclusions
Acupuncture is a preferred option in fibromyalgia patients compared with other ones investigated in our study, as it showed significant improvements in the quality of life, depression, and pain relief. While physiotherapy showed a significant increase in the quality of life only, when compared with sham/placebo. In addition, lidocaine showed no significant improvements in pain reduction or quality of life when compared with sham/placebo.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/healthcare10071176/s1.
Author Contributions
N.M.A. and F.M.H.: idea conception, study design. E.Y.A., J.-D.H., J.-A.L., and G.V.: screening. A.B. and F.A.D.: data extraction. N.M.A. and F.M.H.: quality assessment. E.Y.A. and A.E.-S.A.: analysis. A.B., F.A.D., J.-D.H. and G.V.: manuscript drafting. J.-A.L., A.E.-S.A., and K.-V.C.: supervision. All authors reviewed the manuscript and approved it for publication. J.-A.L. and J.-D.H. contributed equally. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by grants from Hualien Armed Forces General Hospital, Taiwan (HAFGH_A_111002).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The datasets generated during and/or analyzed during the current study are available in the Supplementary Files S2, S3, S4, and S5.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A. The Full Search Strategy of Databases
#1 = (“Acupuncture” OR “Acupuncture Treatment” OR “Acupuncture Treatments” OR “Treatment, Acupuncture” OR “Therapy, Acupuncture” OR “Pharmacoacupuncture Treatment” OR “Pharmacoacupuncture Therapy” OR “Acupotomy” OR “Acupotomies”)
#2 = (“Diet” OR “Diet Therapies” OR “Therapy, Diet” OR “Restrictive Diet Therapies” OR “Restrictive Diet Therapy” OR “Restriction Diet Therapy” OR “Dietary Restriction” OR “Dietary Restrictions” OR “Restriction, Dietary” OR “Dietary Modification” OR “Dietary Modifications” OR “Modification, Dietary” OR “Diet Modification” OR “Diet Modifications” OR “Modification, Diet”)
#3 = (“Lidocaine” OR “2-(Diethylamino)-N-(2,6-Dimethylphenyl)Acetamide” OR “Lignocaine” OR “Lidocaine Carbonate” OR “Lidocaine Hydrocarbonate” OR “Lidocaine Hydrochloride” OR “Xyloneural” OR “Octocaine” OR “Xylocitin”)
#4 = (“Fibromyalgia” OR “Fibromyalgias” OR “Rheumatism, Muscular” OR “Muscular Rheumatism” OR “Fibrositis” OR “Fibromyalgia, Secondary” OR “Secondary Fibromyalgia” OR “Secondary Fibromyalgias” OR “Fibromyalgia, Primary” OR “Primary Fibromyalgia” OR “Primary Fibromyalgias”)
#5 = (#1 OR #2 OR #3)
#6 = (#4 AND #5)
References
- Wolfe, F.; Clauw, D.J.; Fitzcharles, M.A.; Goldenberg, D.L.; Häuser, W.; Katz, R.L.; Mease, P.J.; Russell, A.S.; Russell, I.J.; Walitt, B. 2016 Revisions to the 2010/2011 fibromyalgia diagnostic criteria. Semin. Arthritis Rheum. 2016, 46, 319–329. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clauw, D.J. Fibromyalgia: A clinical review. JAMA 2014, 311, 1547–1555. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldenberg, D.L. Fibromyalgia syndrome. An emerging but controversial condition. JAMA 1987, 257, 2782–2787. [Google Scholar] [CrossRef] [Scilit]
- Rivera, J.; Alegre, C.; Ballina, F.J.; Carbonell, J.; Carmona, L.; Castel, B.; Collado, A.; Esteve, J.J.; Martínez, F.G.; Tornero, J.; et al. Documento de consenso de la Sociedad Española de Reumatología sobre la fibromialgia. Reumatol. Clin. 2006, 2 (Suppl. 1), S55–S66. [Google Scholar] [CrossRef] [Scilit]
- Garrido-Ardila, E.M.; González-López-Arza, M.V.; Jiménez-Palomares, M.; García-Nogales, A.; Rodríguez-Mansilla, J. Effectiveness of acupuncture vs. core stability training in balance and functional capacity of women with fibromyalgia: A randomized controlled trial. Clin. Rehabil. 2020, 34, 630–645. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jones, K.D.; Horak, F.B.; Winters-Stone, K.; Irvine, J.M.; Bennett, R.M. Fibromyalgia is associated with impaired balance and falls. J. Clin. Rheumatol. Pract. Rep. Rheum. Musculoskelet. Dis. 2009, 15, 16–21. [Google Scholar] [CrossRef] [Scilit]
- Arnold, L.M.; Crofford, L.J.; Mease, P.J.; Burgess, S.M.; Palmer, S.C.; Abetz, L.; Martin, S.A. Patient perspectives on the impact of fibromyalgia. Patient Educ. Couns. 2008, 73, 114–120. [Google Scholar] [CrossRef] [Scilit]
- Henriksson, C.M.; Liedberg, G.M.; Gerdle, B. Women with fibromyalgia: Work and rehabilitation. Disabil. Rehabil. 2005, 27, 685–694. [Google Scholar] [CrossRef] [Scilit]
- Jones, J.; Rutledge, D.N.; Jones, K.D.; Matallana, L.; Rooks, D.S. Self-assessed physical function levels of women with fibromyalgia: A national survey. Womens Health Issues 2008, 18, 406–412. [Google Scholar] [CrossRef] [Scilit]
- Wolfe, F.; Anderson, J.; Harkness, D.; Bennett, R.M.; Caro, X.J.; Goldenberg, D.L.; Russell, I.J.; Yunus, M.B. Work and disability status of persons with fibromyalgia. J. Rheumatol. 1997, 24, 1171–1178. [Google Scholar]
- Ablin, J.; Fitzcharles, M.A.; Buskila, D.; Shir, Y.; Sommer, C.; Häuser, W. Treatment of fibromyalgia syndrome: Recommendations of recent evidence-based interdisciplinary guidelines with special emphasis on complementary and alternative therapies. Evid.-Based Complement. Altern. Med. 2013, 2013, 485272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deare, J.C.; Zheng, Z.; Xue, C.C.; Liu, J.P.; Shang, J.; Scott, S.W.; Littlejohn, G. Acupuncture for treating fibromyalgia. Cochrane Database Syst. Rev. 2013, 2013, Cd007070. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Langhorst, J.; Klose, P.; Musial, F.; Irnich, D.; Häuser, W. Efficacy of acupuncture in fibromyalgia syndrome—A systematic review with a meta-analysis of controlled clinical trials. Rheumatology 2010, 49, 778–788. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, S.W.; Wang, W.T.; Yang, T.H.; Liou, T.H.; Chen, G.Y.; Lin, L.F. The balance effect of acupuncture therapy among stroke patients. J. Altern. Complement. Med. 2014, 20, 618–622. [Google Scholar] [CrossRef] [Scilit]
- Sautreuil, P.; Piquemal, M.; Thoumie, P.; Dib, M.; Mailhan, L.; Cobos Romana, R.; Lassaux, A. Sclérose en plaques et neuro-acupuncture. Acupunct. Moxibustion 2011, 10, 40–47. [Google Scholar]
- Lauder, G.R. A review of intravenous lidocaine infusion therapy for paediatric acute and chronic pain management. In Pain Relief–from Analgesics to Alternative Therapies; INTECH: London, UK, 2017; pp. 63–109. [Google Scholar]
- van der Wal, S.E.; van den Heuvel, S.A.; Radema, S.A.; van Berkum, B.F.; Vaneker, M.; Steegers, M.A.; Scheffer, G.J.; Vissers, K.C. The in vitro mechanisms and in vivo efficacy of intravenous lidocaine on the neuroinflammatory response in acute and chronic pain. Eur. J. Pain 2016, 20, 655–674. [Google Scholar] [CrossRef] [Scilit]
- Wilderman, I.; Pugacheva, O.; Perelman, V.S.; Wansbrough, M.C.T.; Voznyak, Y.; Zolnierczyk, L. Repeated Intravenous Lidocaine Infusions for Patients with Fibromyalgia: Higher Doses of Lidocaine Have a Stronger and Longer-Lasting Effect on Pain Reduction. Pain Med. 2020, 21, 1230–1239. [Google Scholar] [CrossRef] [Scilit]
- Haddad, H.W.; Mallepalli, N.R.; Scheinuk, J.E.; Bhargava, P.; Cornett, E.M.; Urits, I.; Kaye, A.D. The Role of Nutrient Supplementation in the Management of Chronic Pain in Fibromyalgia: A Narrative Review. Pain Ther. 2021, 10, 827–848. [Google Scholar] [CrossRef] [Scilit]
- Gill, H.; Perez, C.D.; Gill, B.; El-Halabi, S.; Lee, Y.; Lipsitz, O.; Park, C.; Mansur, R.B.; Rodrigues, N.B.; McIntyre, R.S.; et al. The Prevalence of Suicidal Behaviour in Fibromyalgia Patients. Prog. Neuropsychopharmacol. Biol. Psychiatry 2021, 108, 110078. [Google Scholar] [CrossRef] [Scilit]
- Hutton, B.; Salanti, G.; Caldwell, D.M.; Chaimani, A.; Schmid, C.H.; Cameron, C.; Ioannidis, J.P.; Straus, S.; Thorlund, K.; Jansen, J.P.; et al. The PRISMA extension statement for reporting of systematic reviews incorporating network meta-analyses of health care interventions: Checklist and explanations. Ann. Intern. Med. 2015, 162, 777–784. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G.; Group, T.P. Preferred Reporting Items for Systematic Reviews and Meta-Analyses: The PRISMA Statement. PLoS Med. 2009, 6, e1000097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Monterde, S.; Salvat, I.; Montull, S.; Fernández-Ballart, J. Validación de la versión española del Fibromyalgia Impact Questionnaire. Rev. Esp. Reumatol. 2004, 31, 507–513. [Google Scholar]
- Ware, J.E.J.; Snow, K.; Kosinski, M.; Gandek, B. SF-36 Health Survey Manual and Interprestation Guide; Quality-Metric, Inc.: Lincoln, RI, USA, 2000. [Google Scholar]
- Hawker, G.A.; Mian, S.; Kendzerska, T.; French, M. Measures of adult pain: Visual Analog Scale for Pain (VAS Pain), Numeric Rating Scale for Pain (NRS Pain), McGill Pain Questionnaire (MPQ), Short-Form McGill Pain Questionnaire (SF-MPQ), Chronic Pain Grade Scale (CPGS), Short Form-36 Bodily Pain Scale (SF-36 BPS), and Measure of Intermittent and Constant Osteoarthritis Pain (ICOAP). Arthritis Care Res. 2011, 63 (Suppl. 11), S240–S252. [Google Scholar]
- Wolfe, F.; Clauw, D.J.; Fitzcharles, M.A.; Goldenberg, D.L.; Katz, R.S.; Mease, P.; Russell, A.S.; Russell, I.J.; Winfield, J.B.; Yunus, M.B. The American College of Rheumatology preliminary diagnostic criteria for fibromyalgia and measurement of symptom severity. Arthritis Care Res. 2010, 62, 600–610. [Google Scholar] [CrossRef] [Scilit]
- Burckhardt, C.S.; Clark, S.R.; Bennett, R.M. The fibromyalgia impact questionnaire: Development and validation. J. Rheumatol. 1991, 18, 728–733. [Google Scholar]
- Beck, A.T.; Steer, R.A.; Ball, R.; Ranieri, W.F. Comparison of Beck Depression Inventories-IA and-II in psychiatric outpatients. J. Personal. Assess. 1996, 67, 588–597. [Google Scholar] [CrossRef] [Scilit]
- Radloff, L.S. The CES-D scale: A self-report depression scale for research in the general population. Appl. Psychol. Meas. 1977, 1, 385–401. [Google Scholar] [CrossRef] [Scilit]
- Ramos-Brieva, J.; Cordero-Villafafila, A. A new validation of the Hamilton Rating Scale for Depression. J. Psychiatr. Res. 1988, 22, 21–28. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.; Altman, D.G.; Gøtzsche, P.C.; Jüni, P.; Moher, D.; Oxman, A.D.; Savovic, J.; Schulz, K.F.; Weeks, L.; Sterne, J.A. The Cochrane Collaboration’s tool for assessing risk of bias in randomised trials. BMJ 2011, 343, d5928. [Google Scholar] [CrossRef] [Scilit]
- Yüksel, M.; Ayaş, Ş.; Cabıoğlu, M.T.; Yılmaz, D.; Cabıoğlu, C. Quantitative Data for Transcutaneous Electrical Nerve Stimulation and Acupuncture Effectiveness in Treatment of Fibromyalgia Syndrome. Evid.-Based Complement. Altern. Med. 2019, 2019, 9684649. [Google Scholar] [CrossRef] [Scilit]
- Vlainich, R.; Issy, A.M.; Sakata, R.K. Effect of intravenous lidocaine associated with amitriptyline on pain relief and plasma serotonin, norepinephrine, and dopamine concentrations in fibromyalgia. Clin. J. Pain 2011, 27, 285–288. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vlainich, R.; Issy, A.M.; Gerola, L.R.; Sakata, R.K. Effect of intravenous lidocaine on manifestations of fibromyalgia. Pain Pract. Off. J. World Inst. Pain 2010, 10, 301–305. [Google Scholar] [CrossRef] [Scilit]
- Vas, J.; Santos-Rey, K.; Navarro-Pablo, R.; Modesto, M.; Aguilar, I.; Campos, M.; Aguilar-Velasco, J.F.; Romero, M.; Párraga, P.; Hervás, V.; et al. Acupuncture for fibromyalgia in primary care: A randomised controlled trial. Acupunct. Med. J. Br. Med. Acupunct. Soc. 2016, 34, 257–266. [Google Scholar]
- Uğurlu, F.G.; Sezer, N.; Aktekin, L.; Fidan, F.; Tok, F.; Akkuş, S. The effects of acupuncture versus sham acupuncture in the treatment of fibromyalgia: A randomized controlled clinical trial. Acta Reumatol. Port. 2017, 42, 32–37. [Google Scholar] [PubMed]
- Targino, R.A.; Imamura, M.; Kaziyama, H.H.; Souza, L.P.; Hsing, W.T.; Furlan, A.D.; Imamura, S.T.; Azevedo Neto, R.S. A randomized controlled trial of acupuncture added to usual treatment for fibromyalgia. J. Rehabil. Med. 2008, 40, 582–588. [Google Scholar] [CrossRef] [Scilit]
- Senna, M.K.; Sallam, R.A.; Ashour, H.S.; Elarman, M. Effect of weight reduction on the quality of life in obese patients with fibromyalgia syndrome: A randomized controlled trial. Clin. Rheumatol. 2012, 31, 1591–1597. [Google Scholar] [CrossRef] [Scilit]
- Schweiger, V.; Secchettin, E.; Castellani, C.; Martini, A.; Mazzocchi, E.; Picelli, A.; Polati, E.; Donadello, K.; Valenti, M.T.; Dalle Carbonare, L. Comparison between Acupuncture and Nutraceutical Treatment with Migratens(®) in Patients with Fibromyalgia Syndrome: A Prospective Randomized Clinical Trial. Nutrients 2020, 12, 821. [Google Scholar] [CrossRef] [Scilit]
- Wahner-Roedler, D.L.; Thompson, J.M.; Luedtke, C.A.; King, S.M.; Cha, S.S.; Elkin, P.L.; Bruce, B.K.; Townsend, C.O.; Bergeson, J.R.; Eickhoff, A.L.; et al. Dietary soy supplement on fibromyalgia symptoms: A randomized, double-blind, placebo-controlled, early phase trial. Evid.-Based Complement. Altern. Med. 2011, 2011, 350697. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Posner, I.A. Treatment of Fibromyalgia Syndrome with Intravenous Lidocaine. J. Musculoskelet. Pain 1994, 2, 55–65. [Google Scholar] [CrossRef] [Scilit]
- Mist, S.D.; Jones, K.D. Randomized Controlled Trial of Acupuncture for Women with Fibromyalgia: Group Acupuncture with Traditional Chinese Medicine Diagnosis-Based Point Selection. Pain Med. 2018, 19, 1862–1871. [Google Scholar] [CrossRef] [Scilit]
- San Mauro, I.; Luis, C.-Y.; Sanz Rojo, S.; Sara, L.-O.; Raquel, C.; Ana, M.P.; Elena, G.-V. Short-Time Strategy for Fibromyalgia Treatment Based on Olive Nutraceutical and Inflammatory Gut-Brain Axis Control Diet (IGUBAC) Diet®. Curr. Top. Nutraceutical Res. 2018, 17, 23–32. [Google Scholar]
- Martin, D.P.; Sletten, C.D.; Williams, B.A.; Berger, I.H. Improvement in fibromyalgia symptoms with acupuncture: Results of a randomized controlled trial. Mayo Clin. Proc. 2006, 81, 749–757. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karatay, S.; Okur, S.C.; Uzkeser, H.; Yildirim, K.; Akcay, F. Effects of Acupuncture Treatment on Fibromyalgia Symptoms, Serotonin, and Substance P Levels: A Randomized Sham and Placebo-Controlled Clinical Trial. Pain Med. 2018, 19, 615–628. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Itoh, K.; Kitakoji, H. Effects of acupuncture to treat fibromyalgia: A preliminary randomised controlled trial. Chin. Med. 2010, 5, 11. [Google Scholar] [CrossRef] [Scilit]
- Harris, R.E.; Zubieta, J.K.; Scott, D.J.; Napadow, V.; Gracely, R.H.; Clauw, D.J. Traditional Chinese acupuncture and placebo (sham) acupuncture are differentiated by their effects on mu-opioid receptors (MORs). NeuroImage 2009, 47, 1077–1085. [Google Scholar] [CrossRef] [Scilit]
- Deluze, C.; Bosia, L.; Zirbs, A.; Chantraine, A.; Vischer, T.L. Electroacupuncture in fibromyalgia: Results of a controlled trial. BMJ 1992, 305, 1249–1252. [Google Scholar] [CrossRef] [Scilit]
- Mayhew, E.; Ernst, E. Acupuncture for fibromyalgia—A systematic review of randomized clinical trials. Rheumatology 2007, 46, 801–804. [Google Scholar] [CrossRef] [Scilit]
- Martin-Sanchez, E.; Torralba, E.; Díaz-Domínguez, E.; Barriga, A.; Martin, J.L. Efficacy of acupuncture for the treatment of fibromyalgia: Systematic review and meta-analysis of randomized trials. Open Rheumatol. J. 2009, 3, 25–29. [Google Scholar] [CrossRef] [Scilit]
- Yang, B.; Yi, G.; Hong, W.; Bo, C.; Wang, Z.; Liu, Y.; Xue, Z.; Li, Y. Efficacy of acupuncture on fibromyalgia syndrome: A meta-analysis. J. Tradit. Chin. Med. 2014, 34, 381–391. [Google Scholar]
- Colquhoun, D.; Novella, S.P. Acupuncture Is Theatrical Placebo. Anesth. Analg. 2013, 116, 1360–1363. [Google Scholar] [CrossRef] [Scilit]
- Zhang, X.C.; Chen, H.; Xu, W.T.; Song, Y.Y.; Gu, Y.H.; Ni, G.X. Acupuncture therapy for fibromyalgia: A systematic review and meta-analysis of randomized controlled trials. J. Pain Res. 2019, 12, 527–542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coutaux, A. Non-pharmacological treatments for pain relief: TENS and acupuncture. Jt. Bone Spine 2017, 84, 657–661. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ondrejkovicova, A.; Petrovics, G.; Svitkova, K.; Bajtekova, B.; Bangha, O. Why acupuncture in pain treatment? Neuro Endocrinol. Lett. 2016, 37, 163–168. [Google Scholar] [PubMed]
- Tang, Y.; Yin, H.Y.; Rubini, P.; Illes, P. Acupuncture-Induced Analgesia: A Neurobiological Basis in Purinergic Signaling. Neuroscientist 2016, 22, 563–578. [Google Scholar] [CrossRef] [Scilit]
- Silva, A.R.; Bernardo, A.; Costa, J.; Cardoso, A.; Santos, P.; de Mesquita, M.F.; Vaz Patto, J.; Moreira, P.; Silva, M.L.; Padrão, P. Dietary interventions in fibromyalgia: A systematic review. Ann. Med. 2019, 51 (Suppl. 1), 2–14. [Google Scholar] [CrossRef] [Scilit]
- Nadal-Nicolás, Y.; Miralles-Amorós, L.; Martínez-Olcina, M.; Sánchez-Ortega, M.; Mora, J.; Martínez-Rodríguez, A. Vegetarian and Vegan Diet in Fibromyalgia: A Systematic Review. Int. J. Environ. Res. Public Health 2021, 18, 4955. [Google Scholar] [CrossRef] [Scilit]
- Pagliai, G.; Giangrandi, I.; Dinu, M.; Sofi, F.; Colombini, B. Nutritional Interventions in the Management of Fibromyalgia Syndrome. Nutrients 2020, 12, 2525. [Google Scholar] [CrossRef] [Scilit]
- Albertoni Giraldes, A.L.; Salomão, R.; Leal, P.D.; Brunialti, M.K.; Sakata, R.K. Effect of intravenous lidocaine combined with amitriptyline on pain intensity, clinical manifestations and the concentrations of IL-1, IL-6 and IL-8 in patients with fibromyalgia: A randomized double-blind study. Int. J. Rheum. Dis. 2016, 19, 946–953. [Google Scholar] [CrossRef] [Scilit]









Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).