


Abstract
Heparin remains a foundational parenteral anticoagulant across both acute and chronic care settings. This narrative review summarizes clinical indications and dosing of unfractionated (UFH) and low-molecular-weight heparin (LMWH). It also details laboratory monitoring using activated partial thromboplastin (APTT), anti-factor Xa (anti-Xa), activated clotting time (ACT) and viscoelastic testing (VET), including common pitfalls and interferences. We provide considerations for specific populations as well as complications including heparin resistance, heparin-induced thrombocytopenia (HIT) and heparin reversal strategies. Future research directions include harmonization of therapeutic ranges, mitigation of assay interference and prospective evaluation on monitoring, particular in extracorporeal membrane oxygenation (ECMO), pregnancy and cardiac surgical settings.
1. Introduction
Heparin was first isolated in the early 20th century; despite multiple changes and developments within antithrombotic and anticoagulant therapy, this anticoagulant retains a pivotal role due to its reliability, rapid onset, titratability, reversibility, and monitoring capability [1]. Heparin was originally described by Maurice Doyon in 1910 [2], copurified as an anticoagulant in 1916 [3], and later developed as a clinically used anticoagulant in the 1930s by Charles Best in Canada and Erik Jorpes in Sweden [4]. Unfractionated heparin (UFH) acts by accelerating antithrombin-mediated inhibition of thrombin (factor IIa) and factor Xa [5]. Low-molecular-weight heparin (LMWH), generated by the depolymerization of UFH, exerts a proportionally greater effect on factor Xa, owing to shorter chain length, whilst retaining some of its anti-IIa activity [6]. Pharmacokinetic differences have significant implications: UFH binds to plasma proteins and endothelial cells, resulting in nonlinear, highly variable kinetics among treated patients, often reflected by ~30% bioavailability at therapeutic dosing with a dose-related half-life of ~0.5–1.5 h, thus requiring frequent laboratory monitoring and dose adjustment at therapeutic administration [6]. Conversely, LMWH has less non-specific binding, resulting in more predictable bioavailability and clearance, with ~90–100% bioavailability for enoxaparin, ~80–90% for dalteparin [6] and longer elimination half-life of about ~3–7 h [7], thus enabling fixed or weight-adjusted dosing with the need for monitoring only in limited specific scenarios [8,9,10]. Examples of the most commonly used LMWHs include dalteparin (Fragmin), enoxaparin (Lovenox, Clexane) and tinzaparin (Innohep) [10]. Beyond anticoagulation, heparin exhibits anti-inflammatory and immunomodulatory properties, including interactions with neutrophil extracellular traps (NETs) and complement, though translational clinical impact remains context dependent [11,12]. Accordingly, this review aims to map contemporary evidence on UFH and LMWH pharmacology, complications including HIT and heparin resistance, laboratory monitoring principles and their limitations, and to identify gaps where assay standardization, outcome-linked therapeutic ranges, and clinically accepted applications have limited evidence.
2. Clinical Use of Heparin
2.1. Indications
UFH and LMWH form the backbone of prophylactic and therapeutic anticoagulation and are preferred in many inpatient and some outpatient settings. Both UFH and LMWH can be administered as prophylaxis of venous thromboembolism (VTE) for medium and high-risk patients (including surgical, medical, and orthopedic patients), as well as at therapeutic dosing in management of deep vein thrombosis (DVT), pulmonary embolism (PE) and acute coronary syndrome (ACS) [13,14,15]. Therapeutic dosing of UFH should be considered a high-risk medicine, given its narrow therapeutic window, and that overdosing or underdosing can result in significant adverse patient outcomes in hospitalized patients [16]. UFH is increasingly being replaced as the first-line anticoagulant by LMWH and direct oral anticoagulants (DOACs), especially in patients with atrial fibrillation (AF) for primary or secondary stroke prevention who do not require bridging therapy [17]. UFH is favored when rapid titration, short half-life, reversibility, or procedural control is essential, whereas LMWH is preferred for medically stable VTE and malignancy-associated thrombosis owing to more predictable pharmacodynamics and pharmacokinetics [18]. A comparison of UFH and LMWH is summarized in Table 1.
Table 1.
Comparison of UFH and LMWH.
2.2. Dosing Approaches
Dosing for UFH and LMWH should be divided into prophylactic, therapeutic, and intermediate-dose groups. Prophylactic dosing for UFH is weight-adjusted or fixed dose (2500 IU or 5000 IU) based on twice- or three-times-daily dosing [19], and LMWH is either weight-based (0.5 mg/kg once daily) or fixed-dose regimens (40 mg once daily) [10]. For therapeutic anticoagulation, UFH practice typically involves weight-based nomograms—commonly an initial intravenous bolus of ~80 units/kg followed by 18 units/kg/h—with titration to a single monitoring modality based on activated partial thromboplastin time (APTT) or anti-Xa, which will be discussed later [20]. Therapeutic LMWH is administered subcutaneously using fixed or weight-based regimen (1 mg/kg administered twice daily, or 1.5 mg/kg as a single daily dose). Routine laboratory monitoring for LMWH is unnecessary in most adults, but should be considered in pregnancy, extremes of body weight (<60 kg and >150 kg or BMI > 40 kg/m2), and significant renal impairment [9,10]. There is a lack of consensus regarding dose capping, or setting a maximum dose regardless of total weight, which carries a theoretical risk of underdosing and higher risk of VTE recurrence. In a systemic review by Liu et al. (2023), therapeutic LMWH dosing in obese adults (defined as BMI > 30 kg/m2) found that dose capping resulted in similar VTE recurrence rates (odds ratio (OR): 0.86, 95% confidence interval (CI): 0.11–6.84, p = 0.89), but a lower incidence of bleeding events (OR: 0.30, 95% CI: 0.10–0.89, p = 0.03) [21]. This was not seen in LMWH prophylaxis in obese adults, whereby higher-dose LMWH had a lower incidence of VTE compared with standard-dose regimens (OR: 0.47, 95% CI: 0.27–0.82, p = 0.007) and similar incidence of bleeding events (OR: 0.86, 95% CI: 0.69–1.08, p = 0.020). Intermediate dose of UFH and LMWH has been explored in some patient populations, including coronavirus disease 2019 (COVID-19), but can be considered in patients with DVT or PE or ACS with high bleeding risk or recent/active bleeding [22].
2.3. Complications
Bleeding is the main risk with both UFH and LMWH therapy. Overdose of UFH or LMWH may result in spontaneous or worsening of provoked hemorrhage, which may be life-threatening [10]. Clinical presentations include severe bleeding, compartment syndrome, post-surgical bleeding (including intracranial hemorrhage, hemothorax, retroperitoneal bleeding or intra-abdominal bleeding), disseminated intravascular coagulation (DIC) and multi-organ failure [23]. Overdose or active bleeding may require urgent reversal with protamine or other blood products, which is later discussed. Other complications are less common and include osteoporosis, spontaneous fractures, hypoaldosteronism, hypersensitivity reactions and heparin-induced thrombocytopenia (HIT), sometimes also presenting with thrombosis (HITT) [24,25,26,27,28], which are later discussed in detail. Dalteparin has warnings for its use in pregnant women and neonates due to the preservative benzyl alcohol, which may cause ‘gasping syndrome’, characterized by central nervous system (CNS) depression, gasping and metabolic acidosis in neonates [29,30], although there are preservative-free formulations now available.
2.4. Contraindications
Caution should be had for use of UFH or LMWH in patients with bleeding diathesis, uncontrolled arterial hypertension, recent gastrointestinal bleeding, and diabetic retinopathy, all of which enhance the hemorrhage risk. Caution should also be used in patients with renal impairment, with most guidelines suggesting that LMWH is contraindicated when creatinine clearance (CrCl) falls to <10–15 mL/min [31,32,33].
3. Laboratory Monitoring Modalities
3.1. Activated Partial Thromboplastin Time (APTT)
APTT testing remains widely available and inexpensive, reflecting global intrinsic and common pathway activity [34]. There is substantial reagent and analyzer variability necessitating local calibration of therapeutic range to anti-Xa ~0.3–0.7 IU/mL [35] (Figure 1). An APTT ratio of 2.0–3.5× the laboratory control is often associated with therapeutic UFH, rather than the historical 1.5–2.5× reference range [5,8]. For laboratories unable to perform anti-Xa, the use of less-responsive APTT reagents with a ratio target of ~2.0–3.5× has been proposed as a reasonable surrogate to approximate therapeutic anti-Xa levels, though this remains inferior to assay-specific calibration and should be locally validated [8,36].
Figure 1.
The process of generating an APTT unfractionated heparin (UFH) therapeutic reference range (TRR). (A). The initial data set (n = 111) comprising samples from patients on UFH, preferably with normal prothrombin time (PT) to help exclude capture of hemostasis confounders such as liver disease or factor deficiency. Regression analysis identifies the line of best fit plus 95% confidence intervals. The UFH TRR is interpolated from the anti-Xa range of 0.3–0.7 U/mL, which is 57–94 s in this example. Outlier data points are identified by the red-filled symbols. High-APTT outliers may comprise samples from patients with factor deficiency or lupus anticoagulant. Low-APTT outliers may comprise samples from patients with high factor levels (e.g., fibrinogen, FVIII). These outlier points are removed and the analysis is repeated. (B). After removal of outliers, with n = 104, the UFH TRR does not change markedly (now 54–93 s), and the r2 improves slightly. A second round of outlier points could be identified and were also removed. (C). After removal of these additional outliers, with n = 97, the UFH TRR does not change appreciably (now 53–93 s), and the r2 again improves slightly. The UFH TRR of 53–93 s may be difficult to memorize, and may also suggest an accuracy not present in these evaluations. Therefore, the UFH TRR is adjusted to 50–90 s. Interpolation of these values gives an anti-Xa range of 0.27–0.67 U/mL UFH, which, with rounding, is 0.3–0.7 U/mL, and thus represents an acceptable UFH TRR.
3.2. Anti-Factor Xa (Anti-Xa)
Anti-Xa represents a functional assay that measures chromogen generation proportional to the level of residual factor Xa after neutralization by UFH–antithrombin (AT) complex, and is inversely proportional to the heparin concentration [37]. It should be noted that this assay measures only AT-catalyzed inhibition of factor Xa and does not account for the anti-IIa activity of UFH [38]. Unlike APTT, anti-Xa assays directly quantify heparin–AT inhibition of factor Xa, providing a biochemical target of ~0.3–0.7 IU/mL for UFH, and enabling peak monitoring for LMWH when indicated [38]. A critical caveat is interference from FXa-inhibiting DOACs, which greatly elevate heparin-calibrated anti-Xa values, mandating drug-specific assays or pre-analytical DOAC removal approaches in clinical contexts [39,40]. Beyond ex vivo neutralization, other strategies to remove DOAC effect include timed sampling at the expected trough or after an adequate washout, recognizing that practical windows may exceed 24–48 h because of pharmacokinetic variability, impaired renal function and comedications [40,41]. Anti-Xa monitoring is preferred where a patient’s APTT is abnormal at baseline, which may be due to the presence of a lupus anticoagulant (LA), such as in antiphospholipid syndrome (APS), or in inherited or acquired factor deficiencies (VIII, IX, XI and XII), or in patients not responding to heparin based on APTT [38].
3.3. Activated Clotting Time (ACT)
ACT is a point-of-care (POC) functional whole-blood test commonly used in hospital settings, and is the standard of care for cardiac procedures with large UFH dose administration, as well as non-cardiac vascular surgery. ACT provides largely intraoperative coagulation monitoring [42,43,44,45,46], but may be affected by several patient-related factors (including hypothermia, hemodilution, platelet count, factor deficiencies), all of which may affect heparin under- or overdosing as well as bleeding risk [47]. Multidisciplinary guidelines recommend maintaining ACT at or above 480 s, with acceptance of ≥400 s for devices that employ maximal activation, although there is significant variability between devices and institutional protocols [43,48,49].
3.4. Viscoelastic Testing (VET)
Viscoelastic testing (TEG/ROTEM) provides rapid, whole-blood assessment of clot initiation, propagation, strength, and lysis, integrating platelet and fibrin contributions [50]. Heparin effects can be explored via heparinase channels, or TEG-H; or by comparing INTEM with HEPTEM using ROTEM. While VET is invaluable for bleeding management algorithms in cardiac surgery and critical care, its diagnostic performance for detecting residual heparin after protamine administration is variable, with randomized and observational work showing no clear superiority over ACT and susceptibility to confounding by protamine and heparinase [12,51,52].
3.5. Pre-Analytical Considerations, Interference and Comparison
Accurate interpretation of APTT for heparin monitoring is limited by a number of pre-analytical variables, including heparin contamination and inappropriate sample collection leading to spurious activation of blood coagulation [53], as well as patient-specific factors such as inflammation, high fibrinogen and factor VIII, and the presence of LA, all of which can prolong the clotting time of the assay independent of heparin [54,55]. In particular, if an LA-sensitive APTT reagent is used, the presence of LA can prolong phospholipid-dependent clotting times, complicating APTT-based titration [34]. In this circumstance anti-Xa monitoring is preferable [38]. A theoretical alternative is the use of an LA-insensitive APTT reagent.
As mentioned, common interferences for both APTT and anti-Xa monitoring include concurrent or overlapping anti-Xa DOAC use. Laboratories should provide DOAC-neutralization options (e.g., DOAC-Stop or DOAC-Remove; [39]) or include qualifying statements in their reporting to alert clinicians to potential interactions [40]. Activated-charcoal-based adsorbents including DOAC-Stop and DOAC-Remove remove DOACs ex vivo from citrated plasma and have been validated by mass spectrometry and functional assays to markedly reduce residual apixaban, rivaroxaban, and dabigatran to concentrations unlikely to affect most coagulation tests [56]. Additional pre-analytical factors that may influence both APTT and anti-Xa assays include incorrect timing (non-steady-state sampling or non-peak draws), under-filled citrate tubes, and delayed processing or transcription errors [55].
Viscoelastic testing as a measure of whole-blood coagulation can have interferences from fibrinogen, platelets, and factor compartments affecting interpretability [50]; however, interpretative algorithims and heparin-specific cartridges largely mitigate incorrect interpretation of these, provided there is adequate user-familiarity with the method used. Viscoelastic testing may be an increasingly used adjunct post cardiac surgery, since it already has a growing evidence base including the benefit of reduced blood product use [57,58,59,60,61,62,63,64,65,66,67]. Viscoelastic assays require strict pre-analytical control because whole-blood samples must be tested promptly—ideally within minutes—as delays reduce clot amplitude and distort kinetic parameters [50,68]. Hematocrit, platelet count, and residual heparin markedly alter viscoelastic traces, and inappropriate use of heparinase channels or activators can misrepresent the heparin effect [68,69].
Table 2 summarizes the key differences, limitations and interferences of different assays in UFH and LMWH monitoring.
There have been some reports of transitioning from APTT to anti-Xa monitoring with quicker attainment of therapeutic values, fewer rate changes, and operational efficiencies, although there are no randomized prospective data to guide this [9,70]. Discordance between APTT and anti-Xa is not uncommon, commonly due to elevations in factor VIII/fibrinogen or reductions in factor levels/presence of LA that shorten or prolong APTT disproportionally [70] (Figure 1).
Table 2.
A comparison of heparin monitoring.
4. LMWH and Special Populations
LMWH use has expanded rapidly and has an emerging research base in particular populations. Of note, routine anti-Xa monitoring is not recommended in ‘standard’ patient groups because therapeutic ranges correlated to clinical outcomes are lacking [10,75,76]. Monitoring may be considered in special populations, including pregnancy, renal impairment, extracorporeal membrane oxygenation (ECMO), and extremes of body weight, with standardized peak timing (~4 h post-dose at steady state) and explicit targets for prophylactic versus treatment dosing [9,75,76]. Real-world studies show that many anti-Xa levels are drawn outside the optimal window and that out-of-range values do not consistently drive appropriate dose modifications [77,78].
4.1. Pregnancy
LMWH is the preferred anticoagulant in pregnancy because it does not cross the placenta, has predictable pharmacokinetics, and is associated with low rates of VTE recurrence and adverse events in observational cohorts and systematic reviews [79,80,81]. The guidelines of the American Society of Hematology strongly recommend LMWH over UFH for acute VTE in pregnancy, and also endorses antepartum prophylaxis for women with a history of unprovoked or hormone-associated VTE, with universal emphasis on postpartum prophylaxis if there has been a history of prior VTE [82].
Indications and dosing span prophylactic, intermediate, and therapeutic intensity, selected by baseline risk and clinical presentation, and are weight-based, generally taken from the weight at the beginning of the pregnancy or at the time of the VTE event [82]. Prophylactic LMWH is used for moderate-risk patients (e.g., prior provoked VTE with additional risk factors or certain thrombophilias) and is commonly delivered as fixed low-dose regimens such as enoxaparin 40 mg once daily [82]. The combination of prophylactic-dose LMWH and aspirin in pregnant women with APS has been shown to improve the live birth rate [82,83,84]. Intermediate-dose LMWH (e.g., enoxaparin 40 mg twice daily) is considered for higher-risk patients (e.g., previous unprovoked or estrogen-related VTE), although the Highlow randomized trial found no reduction in recurrent VTE with intermediate- versus low-dose LMWH during pregnancy and six weeks postpartum [84,85,86]. Therapeutic dosing—typically weight-adjusted (e.g., enoxaparin 1 mg/kg twice daily)—is indicated for current VTE, multiple prior VTEs, or high-risk thrombophilia. Nevertheless, UFH may be preferred in select settings such as severe renal impairment or when rapid reversal is anticipated [82,87]. Peripartum management commonly includes stopping anticoagulation 24 h before planned delivery or neuraxial anesthesia. Of note, retrospective data show no significant difference in postpartum hemorrhage with or without conversion from LWMH to UFH peripartum, although some centers continue this practice to facilitate anesthesia management [88,89].
Monitoring for LMWH in pregnacy with anti-Xa activity is controversial and largely based on expert consensus [90,91]. The 2019 European Society of Cardiology [92] and American Society of Hematology 2018 guidelines [82] recommend reserving anti-Xa monitoring for specific high-risk circumstances such as recurrent VTE, renal impairment or extremes of body weight. In high-risk scenarios, anti-Xa monitoring may be performed every 2–4 weeks to maintain trough levels above 0.1 IU/mL and peak levels (4 h post-injection) between 0.5 and 1.0 IU/mL [93].
4.2. Renal Impairment
In patients with renal impairment, the choice between UFH and LMWHs hinges on the differences in elimination and accumulation risk. UFH is largely cleared by reticuloendothelial mechanisms and can be used at standard therapeutic infusion doses across creatinine-clearance ranges [9,94]. In contrast, LMWHs are partly eliminated by the kidneys and can accumulate in patients with lower CrCl, increasing the bleeding risk; most guidelines suggest dose reduction when CrCl < 30 mL/min and consideration of switching to UFH in advanced chronic kidney disease or dialysis-dependent patients [95,96,97]. Enoxaparin therapeutic dosing is typically 1 mg/kg once daily when CrCl < 30 mL/min (versus 1 mg/kg twice daily if CrCl ≥ 30 mL/min), while other LMWHs (e.g., dalteparin, tinzaparin) have variable dose recommendations [32,33,98].
Dose monitoring and drug titration is recommended for patients with renal impairment who require any dose modification or when CrCl < 30 mL/min, with goal peak ranges reported as anti-Xa ~0.5–1.0 IU/mL for twice-daily regimens and trough measurements helping to detect accumulation [78]. After an initial steady-state peak, repeating anti-Xa is only recommended by most guidelines only when clinical status changes (e.g., bleeding, dose changes, or renal function shifts) [78,99]. For enoxaparin in advanced chroncic kideny disease (CKD), prospective and retrospective data show substantial proportions outside the target after the first check—prompting some centers to re-check within 5–7 days or after any dose/renal change, rather than at fixed frequent intervals [99,100]. In severe renal impairment, however, UFH remains preferred over LMWH [94,95].
4.3. ECMO
ECMO is a life support modality for adults and children with life-threatening cardiac and pulmonary failure, allowing temporary oxygenation and blood circulation [101,102]. ECMO exposes the blood compartment to extensive circuitry, leading to contact pathway activation, thrombin generation and consumption of antithrombotic proteins [103]. Often concurrently, critical illness leads to an increase in acute-phase reactants and inflammatory mediators [104,105], causing significant inter- and intra-patient variability in UFH response and assay discordance in these patients [106]. UFH remains recommended as a continuous infusion for all patients receiving ECMO therapy [48,106,107].
ACT has historically been more widely used for heparin monitoring for patients on ECMO [108,109]. Nevertheless, the International Society on Thrombosis and Haemostasis (ISTH) now recommends anti-Xa monitoring, aiming for a target between 0.3 and 0.5 U/mL [73]. Ranucci (2020) has described several issues with using anti-Xa alone in patients receiving ECMO, including interference from bilirubin and free hemoglobin, which can affect chromogenic assay reliability [109]. Alternatively, APTT and VET can be used adjunctively, although they are all susceptible to hypothermia, hemodilution, thrombocytopenia, and LA, as well as acute-phase reactants and assay/device-related factors [75,110,111,112]. For patients with VET, heparin inactivators are typically used, so that the anticoagulant effect can be separated from other factors [50,112]. HIT and heparin resistance have been commonly reported as complications in patients on ECMO, in whom bivalirudin or argatroban may be used, recognizing altered clearance in multi-organ dysfunction and the need for institution-specific protocols [113].
4.4. Extremes of Body Weight
In patients at the extremes of body weight, the pharmacokinetics of parenteral heparins shift in ways that effect efficacy and safety. This includes patients with low body weight (≤45–50 kg or BMI ≤ 18.5 kg/m2) or high body weight (>120 kg or BMI ≥ 40 kg/m2). Current guidelines overall recommend tailored dosing with monitoring [114].
Having a low body weight is associated with higher anti-Xa exposure for patients receiving LMWH. Observational studies of prophylaxis show that reduced-dose enoxaparin (e.g., 20–30 mg once daily) achieves similar VTE outcomes with less bleeding than standard 40 mg daily [115,116,117,118]. For patients with high body weight, LMWH is associated with lower anti-Xa exposure at fixed prophylactic doses [21] although a subsequent meta-analysis suggests that higher prophylactic LMWH doses reduce VTE without increasing bleeding in adult patients, while therapeutic dosing should remain weight-based (actual body weight) rather than capped [119]. A 2024 systematic review of therapeutic enoxaparin reported higher proportions of in-range anti-Xa with reduced weight-based dosing (~0.75–0.85 mg/kg) versus standard ≥ 0.95 mg/kg in patients ≥ 100 kg or BMI ≥ 40 kg/m2, with most bleeding events clustering at standard doses [120]. This, as well as a subsequent review, highlights the need for close anti-Xa monitoring in actual body weight-based dosing in this patient group [121].
For UFH, high body weight can alter the distribution volume of heparin responsiveness, as it is mainly limited to plasma with minimal distribution in adipose tissue [122,123]. Weight-based infusion nomograms are typically used; however, patients with high body weight (BMI ≥ 40 kg/m2) are more likely to exhibit supratherapeutic APTT values compared with non-obese patients when dosing is based on total body weight, highlighting the need for closer laboratory monitoring in this patient group [124,125,126]. In a retrospective audit, George et al. (2020) found that UFH dosing in obese adults (i.e., >150 kg) required lower U/kg/h than in patients < 100 kg (11.6 ± 4.2 vs. 16 ± 4.1, respectively) [127]. In another retrospective study by Nguyen et al. (2025), actual body weight compared with total body weight did not result in a higher likelihood of achieving a therapeutic initial APTT target with UFH (54.2% versus 41.9%, p = 0.238) [128]. When using anti-Xa–based heparin monitoring, Flanagan et al. (2025) found that patients with BMI ≥ 30 kg/m2 achieved therapeutic anti-Xa levels with significantly lower heparin dose (14 units/kg/h vs. 16 units/kg/h, p < 0.001) [129]. Patients in the obese group also had significantly more supratherapeutic anti-Xa levels within the first 24 h (50% vs. 33%, p < 0.0001) and throughout the total duration of UFH therapy (40% vs. 25%, p < 0.0001) without significant differences in bleeding events. A summary of dosing and monitoring strategies is given in Table 3.
Table 3.
Dosing strategies of LMWH in extremes of weight.
4.5. Orthopedic Surgery
In orthopedic surgery, LMWH reduces symptomatic VTE compared with no prophylaxis and performs similarly to rivaroxaban in non-major procedures; trial and meta-analytic data suggest that initiation 6–24 h postoperatively balances bleeding and efficacy without clear superiority of one specific start time [130,131,132,133]. For patients requiring UFH at therapeutic dosing, low-intensity protocols may be utilized in high-risk patients or early postoperatively, which may include omission of bolus, lower APTT (50–60 s) or anti-Xa target (e.g., 0.1–0.3 U/mL) with tight monitoring and early reassessment.
5. Heparin Resistance
5.1. Definitions and Epidemiology
Heparin resistance is most commonly defined as minimal changes in APTT or ACT, or subtherapeutic anti-Xa levels, despite standard or increased UFH dosing (e.g., 35,000 or more units per day), although the threshold dose required is not well defined [16,91,134]. Clinically, heparin resistance refers to inadequate anticoagulation during procedures such as cardiopulmonary bypass despite escalating doses; nevertheless, laboratory-based definitions are increasingly used given variability in dosing scheduling [104,135]. In patients undergoing cardiac bypass, the definition of heparin resistance often used is the need for a dose of over 500 U/kg to achieve an ACT of 400 to 480 s [136]. The epidemiology of this condition varies widely by clinical context, with no universal prevalence due to differing definitions and patient populations, although it is commonly reported to range between 4 and 26% of adult cardiac surgery patients undergoing cardiopulmonary bypass (CPB) [137]. Clinicians may suspect heparin resistance when a therapeutic APTT is not reached within 24 h of heparin infusion. Consideration should be made for testing anti-Xa activity to determine efficacy, and if anti-Xa activity is subtherapeutic, an alternative anticoagulant may be considered [76,138].
5.2. Mechanisms and Management Approaches
Identification of the cause of heparin resistance depends on both clinical and laboratory information, considering that causes may be multifactorial. Because it carries a strong negative charge, heparin commonly binds to many proteins, leading to wide variability in patient response and dose requirements not seen with LMWHs [130]. UFH may bind to plasma proteins commonly elevated in critically ill patients, including acute-phase reactants, factor VIII and fibrinogen, chemokines and cytokines (including platelet factor 4 [PF4], tumor necrosis factor (TNF) and interleukin-8 (IL-8)), von Willebrand factor (VWF), adhesion molecules, microbial and nuclear proteins [104,134]. UFH may also bind to intravenous tubing and ECMO circuit components, potentially contributing to lower-than-expected APTT values by binding AT [139,140,141]. Other causes of heparin resistance include conditions characterized by reduced AT concentration, including congenital AT deficiency, liver disease, acute thrombosis, DIC or consumptive coagulopathy, surgery, hemodialysis or asparaginase use in patients with acute leukemia [142]. Notably, pre-analytic errors should always be a consideration when interpreting a result, particularly when samples are taken from intravenous (heparinized) lines.
When heparin resistance is suspected, a thorough understanding of the patient’s clinical context and status is essential to identify potential causes and determine the indications for current anticoagulation [104]. Initial review of pre-analytical factors should not be omitted, with the consideration of changing to anti-Xa when APTT interference is suspected. Measurement of AT activity can also assist with potential causes. There is no robust evidence that antithrombin concentrate is superior to fresh-frozen plasma (FFP), or that increasing overall heparin dosing is superior in these patients, given that AT levels may fall by approximately 30% after a patient first receives heparin, with levels gradually increasing again over time [104]. In congenital AT deficiency, there is some evidence supporting the use of anti-Xa-based anticoagulation and human recombinant AT for both prophylaxis [143] and as part of VTE therapy [144]. Andexanet alfa acts as a decoy factor Xa molecule, reversing the anticoagulant effects of direct factor Xa inhibitors as well as the indirect inhibitors including LMWH and UFH [145]. Andexanet alfa use in patients undergoing cardiac surgery to reverse apixaban or rivaroxaban often requires markedly increased doses of UFH to achieve target anticoagulation, highlighting another mechanism of heparin resistance [139]. A summary of causes of heparin resistance and management strategies are provided in Table 4.
Table 4.
Causes of heparin resistance and management considerations.
6. Heparin-Induced Thrombocytopenia (HIT)
6.1. Clinical Probability Assessment (4T)
Heparin-induced thrombocytopenia (HIT) is an uncommon but potentially life-threatening complication of heparin therapy, especially if associated with thrombosis (HITT). HIT/HITT reflects an immune-mediated adverse reaction whereby heparin forms complexes with PF4, triggering IgG antibody binding to platelet Fc receptors, leading to platelet cross-linking and activation, thrombosis and thrombocytopenia [146]. Typically, if thrombocytopenia develops or the platelet count falls more than 30 to 50% below the patient’s own baseline over a 5-to-10-day period or 1–3 days with recent exposure, HIT may be suspected. Clinical assessment is essential for all patients with suspected HIT with the 4T score commonly used to assess pre-test probability [147]. The 4T score assists in laboratory and clinical-management-related decisions and assesses the degree of thrombocytopenia, the timing of onset after heparin exposure, thrombosis/other clinical sequelae, and other causes [148]. Although the 4T score can be used to predict the risk of HIT/HITT [149,150,151,152], HIT/HITT can be difficult to exclude or confirm based on clinical information alone, given the high frequency of thrombocytopenia in hospitalized patients [150]. There has been significant inter-observer variability in the use of the 4T score; however, a higher 4T score has remained significantly associated with positive HIT results [151]. In a prospective study, Larsen et al. (2024) found that a substantial number of patients with suspected HIT were misclassified based on the 4T score with a 13.5% false negative rate [152].
6.2. Laboratory Testing and Management Principles
Laboratory testing is essential for HIT/HITT diagnosis, but should not delay the institution of empiric therapy in suspected patients. Two types of assays exist: immunoassays and functional assays [28,153]. Immunoassays detect the presence of anti-PF4/heparin antibodies, while functional assays determine whether these antibodies activate platelets in the presence of heparin and are generally considered diagnostic [154]. Notably, only 10–50% of patients with positive immunoassays have platelet-activating antibodies on functional assays [117]. Because of their low positive predictive value, immunoassays alone cannot confirm or refute a diagnosis of HITT in a suspicious clinical scenario [155,156]. Performing a functional assay following a positive immunoassay is needed to minimize overdiagnosis and inappropriate treatment in patients without HITT [18]. Functional assays are generally considered as gold standards, i.e., 14C-serotonin release assay (14C-SRA) and heparin-induced platelet activation (HIPA). Nevertheless, these tests are limited in their availability, generally have long turnaround times and have a high cost involved [157].
Management of HIT entails cessation of all heparin and initiation of a non-heparin anticoagulant, although prophylactic or therapeutic dosing may vary depending on clinical context and pre-test probability [151]. DOACs may be considered after sufficient platelet recovery, although alternative non-heparin anticoagulants are preferred in the acute phase and depending on patient comorbidities [113,152].
7. Heparin Reversal
Protamine Sulfate
Protamine, the only clinically available UFH reversal agent, binds UFH via electrostatic interactions to form an inactive complex, rapidly neutralizing anticoagulant activity within minutes [158]. Protamine was first described in the 20th century for its ability to neutralize heparin [159] but has also been shown to prolong clotting times when increasing amounts are added to whole blood [160], which was then later understood to exert an effect on platelet function, inhibition of factor V activation and down-regulation of thrombin generation [161]. Common dosing principles are weight- or dose-based titration targeting 1 mg protamine per ~100 U UFH given in the previous 2–3 h, with adjustments for elapsed time [162]. Population pharmacokinetics/pharmacodynamics modeling and perioperative studies of protamine suggest that lower protamine:heparin ratios (approximately 0.6–0.8:1) can achieve biochemical reversal while minimizing protamine excess, though operative contexts and monitoring strategies (ACT vs. anti-Xa) influence dose requirements [163]. In a meta-analysis on routine use of protamine following percutaneous coronary interventions, higher rates of hemostasis success (RR, 1.06; 95% CI [1.01–1.10]; p = 0.01) and shorter hospital length of stay (mean difference (MD), −0.46; 95% CI [−0.65, −0.26]; p < 0.01) were seen in patients who received complete heparin reversal compared with partial or none, highlighting its potential clinical benefit [164]. Post-cardiopulmonary bypass heparin rebound, or the reappearance of heparin anticoagulant activity following protamine reversal, is often demonstrated by increased thrombin time, anti-Xa activity, and ACT and protein-bound heparin levels, which can be mitigated by extended dose strategies [165]. Over-reliance of ACT alone can mask residual anti-Xa activity, supporting the need for multimodal monitoring when precise reversal is critical [161].
Adverse events range from transient hypotension and bradycardia to severe hypersensitivity reactions and anaphylaxis; thus, slow administration is recommended [106,166]. Risk factors include prior protamine exposure, use of protamine-containing insulins, prior vasectomy, rapid infusion, and high doses, though contemporary data suggest fish allergy per se confers low absolute risk and should not be considered a categorical contraindication when reversal is required [158]. Excess protamine may paradoxically impair coagulation via platelet effects and factor V interactions, and caution should thus be taken for prolonged infusions or repeated dosing [167]. Protamine only partially neutralizes LMWH, with more effective anti-IIa reversal and incomplete anti-Xa reversal, and its evidence remains limited [106]. Schroeder et al. (2011) reported that protamine neutralization depends on molecular size, with UFH fragments (mean molecular weight of 15,000 Da) neutralized but LMWH (5000 Da) not neutralized [168]. In vivo and ex vivo studies suggest tinzaparin (higher charge density) is more readily neutralized than enoxaparin, underscoring heterogeneity within the LMWH class [169]. Given only partial reversal, clinical judgment and supportive measures are key in LMWH-associated bleeding.
8. Conclusions and Future Directions
Both UFH and LMWH continue to play an essential role in acute and chronic anticoagulation due to their rapid onset, titratability, and established monitoring frameworks. Across clinical applications, dosing strategies remain highly context-dependent. Despite advances, monitoring practices remain heterogeneous; APTT, anti-Xa, ACT, and viscoelastic testing provide complementary insights, yet each remains an imperfect measure. Special populations—including pregnancy, renal impairment, ECMO, and extremes of body weight—demonstrate significant intra- and inter-patient variability, underscoring the need for individualized dosing and selective monitoring to mitigate bleeding and thrombotic risks. Future research priorities should include the following:
- (1)
- Harmonization of therapeutic targets and laboratory monitoring, particularly the calibration of APTT to anti-Xa and the standardization of anti-Xa monitoring in LMWH therapy, where practice varies widely.
- (2)
- Prospective studies comparing monitoring modalities including viscoelastic testing in high-risk settings such as ECMO.
- (3)
- Clarifying the role of trough monitoring, defining optimal dosing at weight extremes, and larger prospective studies evaluating the role of anti-Xa monitoring during pregnancy, including in prophylactic and therapeutic VTE dosing.
- (4)
- Strengthening evidence-based approaches to heparin resistance and HIT evaluation.
Beyond technical considerations of dosing and assay selection, the safe use of heparin is strongly influenced by systems-level aspects. Effective anticoagulation management relies on close collaboration between clinicians and laboratory services, especially regarding assay selection, sample timing, and the identification of analytical limitations and interferences. Standardized institutional pathways, supported by electronic prescribing, clear laboratory reporting and clinician education, may reduce inappropriate testing and misinterpretation. Future work should hence extend beyond assay performance to include implementation strategies, patient-centered outcomes, and health-system impact, ensuring that advances in heparin monitoring translate into safer and more consistent care across clinical settings.
Author Contributions
Conceptualization, all authors; writing—original draft preparation, B.R.; writing—review and editing, all authors. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
As this manuscript represents a narrative review or synthesis of existing literature, no new data were created.
Acknowledgments
This review represents the authors’ viewpoints and may not reflect those of our associated institutions.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| Anti-Xa | anti-factor Xa |
| ACS | acute coronary syndrome |
| ACT | activated clotting time |
| AF | atrial fibrillation |
| APS | antiphospholipid syndrome |
| APTT | activated partial thromboplastin time |
| CPB | cardiopulmonary bypass |
| CrCl | creatinine clearance |
| CNS | central nervous system |
| DIC | disseminated intravascular coagulation |
| DOACs | direct oral anticoagulants |
| DVT | deep vein thrombosis |
| ECMO | extracorporeal membrane oxygenation |
| HIT | heparin-induced thrombocytopenia |
| HITT | heparin-induced thrombocytopenia with thrombosis |
| FIIa | factor IIa |
| FXa | factor Xa |
| LA | lupus anticoagulant |
| LMWH | low-molecular-weight heparin |
| OR | odds ratios |
| PF4 | platelet factor 4 |
| PE | pulmonary embolism |
| TEG-H | thromboelastography-heparin |
| UFH | unfractionated heparin |
| VET | viscoelastic testing |
| VTE | venous thromboembolism |
References
- Tan, S.; White, H.D.; Layland, J. Heparin use in acute coronary syndromes and cardiovascular interventions: Habit or evidence based? Eur. Heart J. 2022, 43, 1008–1011. [Google Scholar] [CrossRef] [Scilit]
- Doyon, M.; Morel, A.; Policard, A. Estraition directe de l’antithrombine du foie. Influence de la congelation. CR Soc. Biol. Paris 1911, 70. [Google Scholar]
- McLean, J. The thromboplastic action of cephalin. Am. J. Physiol. 1916, 41, 250–257. [Google Scholar] [CrossRef] [Scilit]
- Hogwood, J.; Mulloy, B.; Lever, R.; Gray, E.; Page, C.P. Pharmacology of Heparin and Related Drugs: An Update. Pharmacol. Rev. 2023, 75, 328–379. [Google Scholar] [CrossRef] [Scilit]
- Brill-Edwards, P.; Ginsberg, J.S.; Johnston, M.; Hirsh, J. Establishing a Therapeutic Range for Heparin Therapy. Ann. Intern. Med. 1993, 119, 104–109. [Google Scholar] [CrossRef] [Scilit]
- Fareed, J.; Hoppensteadt, D.; Walenga, J.; Iqbal, O.; Ma, Q.; Jeske, W.; Sheikh, T. Pharmacodynamic and pharmacokinetic properties of enoxaparin: Implications for clinical practice. Clin. Pharmacokinet. 2003, 42, 1043–1057. [Google Scholar] [CrossRef] [Scilit]
- Dunn, C.J.; Sorkin, E.M. Dalteparin sodium: A review of its pharmacology and clinical use in thromboembolic disorders. Drugs 1996, 52, 276–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bates, S.M.; Weitz, J.I.; Johnston, M.; Hirsh, J.; Ginsberg, J.S. Use of a Fixed Activated Partial Thromboplastin Time Ratio to Establish a Therapeutic Range for Unfractionated Heparin. JAMA Intern. Med. 2001, 161, 385–391. [Google Scholar] [CrossRef] [Scilit]
- Hutt-Centeno, E.; Militello, M.; Gomes, M.P. Anti-Xa assays: What is their role today in antithrombotic therapy? Cleve. Clin. J. Med. 2019, 86, 417–427. [Google Scholar] [CrossRef] [Scilit]
- Patel, P.; Varacallo, M.A. Low-Molecular-Weight Heparin (LMWH). In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2025. Available online: https://www.ncbi.nlm.nih.gov/books/NBK525957/ (accessed on 7 March 2026).
- Reardon, B.; Pasalic, L.; Favaloro, E.J. Biomarkers of Coagulation Disorders—Where to from here? Biomolecules 2026, 16, 235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selby, R. ‘TEG talk’: Expanding clinical roles for thromboelastography and ROTEM. Hematol. ASH Educ. Program 2020, 2020, 67–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, K.; Song, Y.; Li, X.; Ding, J.; Gao, Z.; Lu, D.; Zhu, Y. Pentasaccharides for the prevention of venous thromboembolism. Cochrane Database Syst. Rev. 2016, 10, CD005134. [Google Scholar] [CrossRef] [Scilit]
- Bhave, A.; Dumra, H.; Bansal, S. Management of Acute Pulmonary Embolism: A Review. J. Assoc. Physicians India 2024, 72, 80–91. [Google Scholar] [CrossRef] [Scilit]
- Alturkmani, H.; Uretsky, B.; Patel, S.; Albadaineh, M.; Alqaisi, O.; Alaiwah, M.; Cross, M.; Abbasi, D.; Rollefson, W. Safety and Efficacy of Enoxaparin During Low-Risk Elective Percutaneous Coronary Intervention. Am. J. Cardiol. 2024, 218, 63–67. [Google Scholar] [CrossRef] [Scilit]
- Intravenous Unfractionated Heparin Infusion. Clinical Excellence Commission (CEC) Guidelines. 2025. Available online: https://www1.health.nsw.gov.au/pds/Pages/doc.aspx?dn=GL2025_009 (accessed on 7 February 2026).
- Yaghi, S.; Mistry, E.; Liberman, A.L.; Giles, J.; Asad, S.D.; Liu, A.; Nagy, M.; Kaushal, A.; Azher, I.; Mac Grory, B.; et al. Anticoagulation Type and Early Recurrence in Cardioembolic Stroke: The IAC Study. Stroke 2020, 51, 2724–2732. [Google Scholar] [CrossRef] [Scilit]
- Linkins, L.A.; Dans, A.L.; Moores, L.K.; Bona, R.; Davidson, B.L.; Schulman, S.; Crowther, M. Treatment and prevention of heparin-induced thrombocytopenia: Antithrombotic therapy and prevention of thrombosis: American College of Chest Physicians evidence-based clinical practice guidelines. Chest J. 2012, 141, e495S–e530S. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- King, C.S.; Holley, A.B.; Jackson, J.L.; Shorr, A.F.; Moores, L.K. Twice vs three times daily heparin dosing for thromboembolism prophylaxis in the general medical population: A metaanalysis. Chest 2007, 131, 507–516. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burnett, A.E. Nomogram for Adjusting UFH Using Anti-Xa or APTT. UpToDate Image Resource. 2025. Available online: https://www.uptodate.com/contents/image?imageKey=HEME%2F122945 (accessed on 7 February 2026).
- Liu, J.; Qiao, X.; Wu, M.; Wang, H.; Luo, H.; Zhang, H.; Chen, Y.; Sun, J.; Tang, B. Strategies involving low-molecular-weight heparin for the treatment and prevention of venous thromboembolism in patients with obesity: A systematic review and meta-analysis. Front. Endocrinol. 2023, 14, 1084511. [Google Scholar] [CrossRef] [Scilit]
- Bonfim, L.C.M.G.; Guerini, I.S.; Zambon, M.G.; Pires, G.B.; Silva, A.C.F.; Gobatto, A.L.N.; Lopes, M.A.; Brosnahan, S.B. Optimal dosing of heparin for prophylactic anticoagulation in critically ill COVID-19 patients a systematic review and meta-analysis of randomized controlled trials. J. Crit. Care 2023, 77, 154344. [Google Scholar] [CrossRef] [Scilit]
- Lu, C.; Crowther, M.A.; Mithoowani, S. Management of intentional overdose of low-molecular-weight heparin. Cmaj 2022, 194, E122–E125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prince, M.; Wenham, T. Heparin-induced thrombocytopaenia. Postgrad. Med. J. 2018, 94, 453–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gajic-Veljanoski, O.; Phua, C.W.; Shah, P.S.; Cheung, A.M. Effects of Long-Term Low-Molecular-Weight Heparin on Fractures and Bone Density in Non-Pregnant Adults: A Systematic Review with Meta-Analysis. J. Gen. Intern. Med. 2016, 31, 947–957. [Google Scholar] [CrossRef] [Scilit]
- Levesque, H.; Verdier, S.; Cailleux, N.; Elie-Legrand, M.C.; Gancel, A.; Basuyau, J.P.; Borg, J.Y.; Moore, N.; Courtois, H. Low molecular weight heparins and hypoaldosteronism. BMJ 1990, 300, 1437–1438. [Google Scholar] [CrossRef] [Scilit]
- Cesana, P.; Scherer, K.; Bircher, A.J. Immediate Type Hypersensitivity to Heparins: Two Case Reports and a Review of the Literature. Int. Arch. Allergy Immunol. 2016, 171, 285–289. [Google Scholar] [CrossRef] [Scilit]
- Favaloro, E.J.; Pasalic, L.; Lippi, G. Antibodies against Platelet Factor 4 and Their Associated Pathologies: From HIT/HITT to Spontaneous HIT-Like Syndrome, to COVID-19, to VITT/TTS. Antibodies 2022, 11, 7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dabbous, M.K.; Sakr, F.R.; Malaeb, D.N. Anticoagulant therapy in pediatrics. J. Basic Clin. Pharm. 2014, 5, 27–33. [Google Scholar] [CrossRef] [Scilit]
- Damle, B.; Jen, F.; Sherman, N.; Jani, D.; Sweeney, K. Population Pharmacokinetic Analysis of Dalteparin in Pediatric Patients With Venous Thromboembolism. J. Clin. Pharmacol. 2021, 61, 172–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lim, W.; Dentali, F.; Eikelboom, J.W.; Crowther, M.A. Low-molecular-weight heparin in patients with chronic renal insufficiency. Ann. Pharmacother. 2008, 42, 847–857. [Google Scholar] [CrossRef] [Scilit]
- Gouin-Thibault, I.; Pautas, E.; Siguret, V. Safety profile of different low-molecular weight heparins used at therapeutic dose. Drug Saf. 2005, 28, 333–349. [Google Scholar] [CrossRef] [Scilit]
- Hughes, S.; Szeki, I.; Nash, M.J.; Thachil, J. Anticoagulation in chronic kidney disease patients—The practical aspects. Clin. Kidney J. 2014, 7, 442–449. [Google Scholar] [CrossRef] [Scilit]
- Favaloro, E.J.; Kershaw, G.; Mohammed, S.; Lippi, G. How to Optimize Activated Partial Thromboplastin Time (APTT) Testing: Solutions to Establishing and Verifying Normal Reference Intervals and Assessing APTT Reagents for Sensitivity to Heparin, Lupus Anticoagulant, and Clotting Factors. Semin. Thromb. Hemost. 2019, 45, 22–35. [Google Scholar] [CrossRef] [Scilit]
- Favaloro, E.J.; Mohammed, S.; Vong, R.; McVicker, W.; Chapman, K.; Swanepoel, P.; Kershaw, G.; Cai, N.; Just, S.; Connelly, L.; et al. Verification of the ACL Top 50 family (350, 550 and 750) for harmonization of routine coagulation assays in a large network of 60 laboratories. Am. J. Clin. Pathol. 2021, 156, 661–678. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cuker, A.; Ptashkin, B.; Konkle, B.A.; Pipe, S.W.; Whinna, H.C.; Zheng, X.L.; Cines, D.B.; Pollak, E.S. Interlaboratory agreement in the monitoring of unfractionated heparin using the anti-factor Xa-correlated activated partial thromboplastin time. J. Thromb. Haemost. 2009, 7, 80–86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laposata, M.; Green, D.; Van Cott, E.M.; Barrowcliffe, T.W.; Goodnight, S.H.; Sosolik, R.C. College of American pathologists conference XXXI on laboratory monitoring of anticoagulant therapy. Laboratory monitoring of unfractionated heparin therapy. Arch. Pathol. Lab. Med. 1998, 122, 782–798. [Google Scholar]
- Safani, M.; Appleby, S.; Chiu, R.; Favaloro, E.J.; Ferro, E.T.; Johannes, J.; Sheth, M. Application of anti-Xa assay in monitoring unfractionated heparin therapy in contemporary antithrombotic management. Expert. Rev. Hematol. 2023, 16, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Douxfils, J.; Adcock, D.; Bates, S.M.; Favaloro, E.J.; Gouin-Thibault, I.; Guillermo, C.; Kawai, Y.; Lindhoff-Last, P.D.E.; Kitchen, S.; Gosselin, R.C. 2021 Update of the International Council for Standardization in Haematology Recommendations for Laboratory Measurement of Direct Oral Anticoagulants. Thromb Haemost. 2021, 121, 1008–1020. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moser, K.A.; Smock, K.J. DOAC interference in hemostasis assays. Hematol. ASH Educ. Program 2021, 2021, 129–133. [Google Scholar] [CrossRef] [Scilit]
- Mithoowani, S.; Siegal, D. DOACs: Role of anti-Xa and drug level monitoring. Hematology 2024, 2024, 178–185. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Serrick, C.; Rao, V.; Yip, P.M. A comparative analysis of four activated clotting time measurement devices in cardiac surgery with cardiopulmonary bypass. Perfusion 2021, 36, 610–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thompson, T.Z.; Kunak, R.L.; Savage, N.M.; Agarwal, S.; Chazelle, J.; Singh, G. Intraoperative Monitoring of Heparin: Comparison of Activated Coagulation Time and Whole Blood Heparin Measurements by Different Point-of-Care Devices with Heparin Concentration by Laboratory-Performed Plasma Anti-Xa Assay. Lab. Med. 2019, 50, 348–356. [Google Scholar] [CrossRef] [Scilit]
- Despotis, G.J.; Joist, J.H.; Hogue, C.W., Jr.; Alsoufiev, A.; Kater, K.; Goodnough, L.T.; Santoro, S.A.; Spitznagel, E.; Rosenblum, M.; Lappas, D.G. The impact of heparin concentration and activated clotting time monitoring on blood conservation. A prospective, randomized evaluation in patients undergoing cardiac operation. J. Thorac. Cardiovasc. Surg. 1995, 110, 46–54. [Google Scholar] [CrossRef] [Scilit]
- Despotis, G.J.; Joist, J.H.; Hogue, C.W., Jr.; Alsoufiev, A.; Joiner-Maier, D.; Santoro, S.A.; Spitznagel, E.; Weitz, J.I.; Goodnough, L.T. More effective suppression of hemostatic system activation in patients undergoing cardiac surgery by heparin dosing based on heparin blood concentrations rather than ACT. Thromb. Haemost. 1996, 76, 902–908. [Google Scholar] [CrossRef] [Scilit]
- Doganer, O.; Wiersema, A.M.; Pierie, M.; Blankensteijn, J.D.; Yeung, K.K.; Jongkind, V. More Effective Anticoagulation During Non-Cardiac Arterial Procedures Using Activated Clotting Time Guided Heparin Administration. Ann. Vasc. Surg. 2021, 76, 378–388. [Google Scholar] [CrossRef] [Scilit]
- Finley, A.; Greenberg, C. Heparin sensitivity and resistance: Management during cardiopulmonary bypass. Anesth. Analg. 2013, 116, 1210–1222. [Google Scholar] [CrossRef] [Scilit]
- Shore-Lesserson, L.; Baker, R.A.; Ferraris, V.; Greilich, P.E.; Fitzgerald, D.; Roman, P.; Hammon, J. STS/SCA/AmSECT Clinical Practice Guidelines: Anticoagulation during Cardiopulmonary Bypass. J. Extra Corpor. Technol. 2018, 50, 5–18. [Google Scholar] [CrossRef] [Scilit]
- Dirkmann, D.; Nagy, E.; Britten, M.W.; Peters, J. Point-of-care measurement of activated clotting time for cardiac surgery as measured by the Hemochron signature elite and the Abbott i-STAT: Agreement, concordance, and clinical reliability. BMC Anesthesiol. 2019, 19, 174. [Google Scholar] [CrossRef] [Scilit]
- Reardon, B.; Pasalic, L.; Favaloro, E.J. The Role of Viscoelastic Testing in Assessing Hemostasis: A Challenge to Standard Laboratory Assays? J. Clin. Med. 2024, 13, 3612. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levin, A.I.; Heine, A.M.; Coetzee, J.F.; Coetzee, A. Heparinase thromboelastography compared with activated coagulation time for protamine titration after cardiopulmonary bypass. J. Cardiothorac. Vasc. Anesth. 2014, 28, 224–229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meesters, M.I.; Lancé, M.D.; van der Steeg, R.; Boer, C. The value of the thromboelastometry heparinase assay (HEPTEM) in cardiac surgery. Thromb. Haemost. 2015, 114, 1058–1063. [Google Scholar] [CrossRef] [Scilit]
- Favaloro, E.J.; Funk, D.M.; Lippi, G. Preanalytical variables in coagulation testing associated to diagnostic errors in hemostasis. Lab. Med. 2012, 43, 54–60. [Google Scholar] [CrossRef] [Scilit]
- Thalappil, V.; Anand, J.; Keepanasseril, A.; Kar, R. Standardization of Anti-Xa Assay and its Comparison with Activated Partial Thromboplastin Time for Monitoring Unfractionated Heparin Therapy. Indian J. Hematol. Blood Transfus. 2024, 40, 432–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- May, J.E.; Siniard, R.C.; Taylor, L.J.; Marques, M.B.; Gangaraju, R. From Activated Partial Thromboplastin Time to Antifactor Xa and Back Again. Am. J. Clin. Pathol. 2022, 157, 321–327. [Google Scholar] [CrossRef] [Scilit]
- Slavik, L.; Jacova, J.; Friedecky, D.; Ulehlova, J.; Tauber, Z.; Prochazkova, J.; Hlusi, A.; Palova, M. Evaluation of the DOAC-Stop Procedure by LC-MS/MS Assays for Determining the Residual Activity of Dabigatran, Rivaroxaban, and Apixaban. Clin. Appl. Thromb. Hemost. 2019, 25, 1076029619872556. [Google Scholar] [CrossRef] [Scilit]
- Serraino, G.F.; Murphy, G.J. Routine use of viscoelastic blood tests for diagnosis and treatment of coagulopathic bleeding in cardiac surgery: Updated systematic review and meta-analysis. Br. J. Anaesth. 2017, 118, 823–833. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wikkelsø, A.; Wetterslev, J.; Møller, A.M.; Afshari, A. Thromboelastography (TEG) or thromboelastometry (ROTEM) to monitor haemostatic treatment versus usual care in adults or children with bleeding. Cochrane Database Syst. Rev. 2016, 2016, CD007871. [Google Scholar] [CrossRef] [Scilit]
- Karkouti, K.; Callum, J.; Wijeysundera, D.N.; Rao, V.; Crowther, M.; Grocott, H.P.; Pinto, R.; Scales, D.C.; TACS Investigators. Point-of-Care Hemostatic Testing in Cardiac Surgery: A Stepped-Wedge Clustered Randomized Controlled Trial. Circulation 2016, 134, 1152–1162. [Google Scholar] [CrossRef] [Scilit]
- Li, C.; Zhao, Q.; Yang, K.; Jiang, L.; Yu, J. Thromboelastography or rotational thromboelastometry for bleeding management in adults undergoing cardiac surgery: A systematic review with meta-analysis and trial sequential analysis. J. Thorac. Dis. 2019, 11, 1170–1181. [Google Scholar] [CrossRef] [Scilit]
- Meco, M.; Montisci, A.; Giustiniano, E.; Greco, M.; Pappalardo, F.; Mammana, L.; Panisi, P.; Roscitano, C.; Cirri, S.; Donatelli, F.; et al. Viscoelastic Blood Tests Use in Adult Cardiac Surgery: Meta-Analysis, Meta-Regression, and Trial Sequential Analysis. J. Cardiothorac. Vasc. Anesth. 2020, 34, 119–127. [Google Scholar] [CrossRef] [Scilit]
- Deppe, A.C.; Weber, C.; Zimmermann, J.; Kuhn, E.W.; Slottosch, I.; Liakopoulos, O.J.; Choi, Y.H.; Wahlers, T. Point-of-care thromboelastography/thromboelastometry-based coagulation management in cardiac surgery: A meta-analysis of 8332 patients. J. Surg. Res. 2016, 203, 424–433. [Google Scholar] [CrossRef] [Scilit]
- Kuiper, G.J.A.J.M.; van Egmond, L.T.; Henskens, Y.M.C.; Roekaerts, P.M.; Maessen, J.G.; Ten Cate, H.; Buhre, W.F.; Lancé, M.D. Shifts of Transfusion Demand in Cardiac Surgery After Implementation of Rotational Thromboelastometry-Guided Transfusion Protocols: Analysis of the HEROES-CS (HEmostasis Registry of patiEntS in Cardiac Surgery) Observational, Prospective Open Cohort Database. J. Cardiothorac. Vasc. Anesth. 2019, 33, 307–317. [Google Scholar] [CrossRef] [Scilit]
- Santos, A.S.; Oliveira, A.J.F.; Barbosa, M.C.L.; Nogueira, J.L.D.S. Viscoelastic haemostatic assays in the perioperative period of surgical procedures: Systematic review and meta-analysis. J. Clin. Anesth. 2020, 64, 109809. [Google Scholar] [CrossRef] [Scilit]
- Rahe-Meyer, N.; Solomon, C.; Winterhalter, M.; Piepenbrock, S.; Tanaka, K.; Haverich, A.; Pichlmaier, M. Thromboelastometry-guided administration of fibrinogen concentrate for the treatment of excessive intraoperative bleeding in thoracoabdominal aortic aneurysm surgery. J. Thorac. Cardiovasc. Surg. 2009, 138, 694–702. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bolliger, D.; Lancé, M.D.; Siegemund, M. Point-of-Care Platelet Function Monitoring: Implications for Patients With Platelet Inhibitors in Cardiac Surgery. J. Cardiothorac. Vasc. Anesth. 2021, 35, 1049–1059. [Google Scholar] [CrossRef] [Scilit]
- Erdoes, G.; Ahmed, A.; Kurz, S.D.; Gerber, D.; Bolliger, D. Perioperative hemostatic management of patients with type A aortic dissection. Front. Cardiovasc. Med. 2023, 10, 1294505. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knudsen, K. ROTEM and TEG in ICU: Hemostasis Monitoring. The Anesthesia Guide. Updated 2025. Available online: https://anesthguide.com/topic/rotem-teg-and-multiplate/ (accessed on 6 March 2026).
- Levy, J.H.; Welsby, I. Viscoelastic Testing for Perioperative Bleeding Management. Hematologist 2025, 22. [Google Scholar] [CrossRef] [Scilit]
- Vandiver, J.W.; Vondracek, T.G. Antifactor Xa levels versus activated partial thromboplastin time for monitoring unfractionated heparin. Pharmacotherapy 2012, 32, 546–558. [Google Scholar] [CrossRef] [Scilit]
- Opoku, A.; Iwuji, K.; Clough, B.; Le, J.; Moore, M.; Simmons, C.; Hyde, B. Discordance between aPTT and anti-Xa levels in IV UFH therapy. Southwest Respir. Crit. Care Chron. 2019, 7, 12–18. [Google Scholar] [CrossRef] [Scilit]
- Smythe, M.A.; Mattson, J.C.; Koerber, J.M. The heparin anti-Xa therapeutic range: Are we there yet? Chest 2002, 121, 303–304. [Google Scholar] [CrossRef] [Scilit]
- Helms, J.; Frere, C.; Thiele, T.; Tanaka, K.A.; Neal, M.D.; Steiner, M.E.; Connors, J.M.; Levy, J.H. Anticoagulation in adult patients supported with extracorporeal membrane oxygenation: Guidance from the Scientific and Standardization Committees on Perioperative and Critical Care Haemostasis and Thrombosis of the International Society on Thrombosis and Haemostasis. J. Thromb. Haemost. 2023, 21, 373–396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rajsic, S.; Breitkopf, R.; Treml, B.; Jadzic, D.; Innerhofer, N.; Eckhardt, C.; Oberleitner, C.; Nawabi, F.; Bukumiric, Z. Anti-Xa-guided Anticoagulation With Unfractionated Heparin and Thrombosis During Extracorporeal Membrane Oxygenation Support: A Systematic Review and Meta-analysis. J. Cardiothorac. Vasc. Anesth. 2024, 38, 1662–1672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levy, J.H.; Staudinger, T.; Steiner, M.E. How to manage anticoagulation during ECMO. Intensive Care Med. 2022, 48, 1076–1079. [Google Scholar] [CrossRef] [Scilit]
- Garcia, D.A.; Baglin, T.P.; Weitz, J.I.; Samama, M.M. Parenteral anticoagulants: Antithrombotic Therapy and Prevention of Thrombosis, 9th ed: American College of Chest Physicians Evidence-Based Clinical Practice Guidelines. Chest 2012, 141, e24S–e43S. [Google Scholar] [CrossRef] [Scilit]
- Lin, A.; Vazquez, S.R.; Jones, A.E.; Witt, D.M. Description of anti-Xa monitoring practices during LMWH use. J. Thromb. Thrombolysis 2019, 48, 623–628. [Google Scholar] [CrossRef] [Scilit]
- Quesep, N.; Menendez, L.; Dittmar, E.; Gopalani, R.B.; Patel, P.; Nagalla, S. LMWH Anti-Xa Level Monitoring in a Healthcare System. Blood 2022, 140, 11374. [Google Scholar] [CrossRef] [Scilit]
- Greer, I.A.; Nelson-Piercy, C. Low-molecular-weight heparins for thromboprophylaxis and treatment of venous thromboembolism in pregnancy: A systematic review of safety and efficacy. Blood 2005, 106, 401–407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kearsley, R.; Stocks, G. Venous thromboembolism in pregnancy-diagnosis, management, and treatment. BJA Educ. 2021, 21, 117–123. [Google Scholar] [CrossRef] [Scilit]
- Bassa, B.A.; Cutts, B.; Ainle, F.N. Insights into antithrombotic therapy in pregnancy. Lancet Haematol. 2024, 11, e881–e882. [Google Scholar] [CrossRef] [Scilit]
- Bates, S.M.; Rajasekhar, A.; Middeldorp, S.; McLintock, C.; Rodger, M.A.; James, A.H.; Vazquez, S.R.; Greer, I.A.; Riva, J.J.; Bhatt, M.; et al. American Society of Hematology 2018 guidelines for management of venous thromboembolism: Venous thromboembolism in the context of pregnancy. Blood Adv. 2018, 2, 3317–3359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- American College of Obstetricians and Gynecologists. ACOG Practice Bulletin No. 196: Thromboembolism in Pregnancy. Obstet. Gynecol. 2018, 132, e1–e17. [Google Scholar] [CrossRef] [Scilit]
- Hamulyák, E.N.; Scheres, L.J.; Marijnen, M.C.; Goddijn, M.; Middeldorp, S. Aspirin or heparin or both for improving pregnancy outcomes in women with persistent antiphospholipid antibodies and recurrent pregnancy loss. Cochrane Database Syst. Rev. 2020, 5, CD012852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laskin, C.A.; Spitzer, K.A.; Clark, C.A.; Crowther, M.R.; Ginsberg, J.S.; Hawker, G.A.; Kingdom, J.C.; Barrett, J.; Gent, M. Low molecular weight heparin and aspirin for recurrent pregnancy loss: Results from the randomized, controlled HepASA Trial. J. Rheumatol. 2009, 36, 279–287. [Google Scholar] [CrossRef] [Scilit]
- Bistervels, I.M.; Buchmüller, A.; Wiegers, H.M.G.; Ní Áinle, F.; Tardy, B.; Donnelly, J.; Verhamme, P.; Jacobsen, A.F.; Hansen, A.T.; Rodger, M.A.; et al. Intermediate-dose versus low-dose low-molecular-weight heparin in pregnant and post-partum women with a history of venous thromboembolism (Highlow study): An open-label, multicentre, randomised, controlled trial. Lancet 2022, 400, 1777–1787. [Google Scholar] [CrossRef] [Scilit]
- Tseng, E. Clarifying Indications and Dosing of Anticoagulants in Pregnancy. Hematologist 2023, 20, 1. [Google Scholar] [CrossRef] [Scilit]
- Bain, E.; Wilson, A.; Tooher, R.; Gates, S.; Davis, L.J.; Middleton, P. Prophylaxis for venous thromboembolic disease in pregnancy and the early postnatal period. Cochrane Database Syst. Rev. 2014, CD001689, Erratum in Cochrane Database Syst. Rev. 2021, 3, CD001689. https://doi.org/10.1002/14651858.CD001689.pub4. [Google Scholar] [CrossRef] [Scilit]
- Leffert, L.R.; Dubois, H.M.; Butwick, A.J.; Carvalho, B.; Houle, T.T.; Landau, R. Neuraxial Anesthesia in Obstetric Patients Receiving Thromboprophylaxis with Unfractionated or Low-Molecular-Weight Heparin: A Systematic Review of Spinal Epidural Hematoma. Anesth. Analg. 2017, 125, 223–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cordes, S.A.; Faysal, H.; Calderon, J.A.; Li, R.; Gelfand, S.T.; Felfeli, M.; Kim, H.; Ahmadzia, H.K. Evaluating clinical outcomes related to the administration of low-molecular-weight heparin and unfractionated heparin in pregnant patients prior to delivery. SN Compr. Clin. Med. 2024, 7, 9. [Google Scholar] [CrossRef] [Scilit]
- Hirsh, J.; Bauer, K.A.; Donati, M.B.; Gould, M.; Samama, M.M.; Weitz, J.I. Parenteral anticoagulants: American College of Chest Physicians evidence-based clinical practice guidelines (8th edition). Chest 2008, 133, 141S–159S. [Google Scholar] [CrossRef] [Scilit]
- Konstantinides, S.V.; Meyer, G.; Becattini, C.; Bueno, H.; Geersing, G.J.; Harjola, V.P.; Huisman, M.V.; Humbert, M.; Jennings, C.S.; Jiménez, D.; et al. 2019 ESCGuidelines for the diagnosis management of acute pulmonary embolism developed in collaboration with the European Respiratory Society (ERS). Eur. Heart J. 2020, 41, 543–603. [Google Scholar] [CrossRef] [Scilit]
- Bramham, K.; Retter, A.; Robinson, S.E.; Mitchell, M.; Moore, G.W.; Hunt, B.J. How I treat heterozygous hereditary antithrombin deficiency in pregnancy. Thromb. Haemost. 2013, 110, 550–559. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takemoto, C.M.; Streiff, M.B.; Shermock, K.M.; Kraus, P.S.; Chen, J.; Jani, J.; Kickler, T. Activated partial thromboplastin time and anti-xa measurements in heparin monitoring: Biochemical basis for discordance. Am. J. Clin. Pathol. 2013, 139, 450–456. [Google Scholar] [CrossRef] [Scilit]
- Ribic, C.; Crowther, M. Thrombosis and anticoagulation in the setting of renal or liver disease. Hematol. Am. Soc. Hematol. Educ. Program 2016, 2016, 188–195. [Google Scholar] [CrossRef] [Scilit]
- Stevens, S.M.; Woller, S.C.; Baumann Kreuziger, L.; Doerschug, K.; Geersing, G.J.; Klok, F.A.; King, C.S.; Murin, S.; Vintch, J.R.E.; Wells, P.S.; et al. Antithrombotic Therapy for VTE Disease: Compendium and Review of CHEST Guidelines 2012–2021. Chest 2024, 166, 388–404. [Google Scholar] [CrossRef] [Scilit]
- van den Broek, M.P.H.; Verschueren, M.V.; Knibbe, C.A.J. Critical appraisal of evidence for anti-Xa monitoring and dosing of low-molecular-weight heparin in renal insufficiency. Expert. Rev. Clin. Pharmacol. 2022, 15, 1155–1163. [Google Scholar] [CrossRef] [Scilit]
- NHS Greater Glasgow & Clyde. Heparin Dose Adjustment in the Presence of Renal Impairment (Adult, Non-Pregnant). Version 6, September 2023. Available online: www.rightdecisions.scot.nhs.uk/media/svvhvt21/heparin-dose-adjustment-157.pdf (accessed on 8 February 2026).
- Vega, J.A.; Lee, Y.R.; McMahan, D.; Duong, H.N.Q. Monitoring enoxaparin with anti-factor Xa levels in severe renal impairment. Clin. Pharmacol. Biopharm. 2016, 3, 1000113. [Google Scholar]
- Cases Corona, C.M.; López Melero, E.; Landaluce Triska, E. Enoxaparin dosing in advanced chronic kidney disease: Importance of monitoring with anti-Xa levels. Nephrol. Dial. Transplant. 2024, 39, gfae069-1446. [Google Scholar] [CrossRef] [Scilit]
- Richardson, A.S.C.; Tonna, J.E.; Nanjayya, V.; Nixon, P.; Abrams, D.C.; Raman, L.; Bernard, S.; Finney, S.J.; Grunau, B.; Youngquist, S.T.; et al. Extracorporeal Cardiopulmonary Resuscitation in Adults. Interim. Guideline Consensus Statement From the Extracorporeal Life Support. Organization. ASAIO J. 2021, 67, 221–228. [Google Scholar] [CrossRef] [Scilit]
- Bartlett, R.; Arachichilage, D.J.; Chitlur, M.; Hui, S.R.; Neunert, C.; Doyle, A.; Retter, A.; Hunt, B.J.; Lim, H.S.; Saini, A.; et al. The History of Extracorporeal Membrane Oxygenation and the Development of Extracorporeal Membrane Oxygenation Anticoagulation. Semin. Thromb. Hemost. 2024, 50, 81–90. [Google Scholar] [CrossRef] [Scilit]
- Oliver, W.C. Anticoagulation and coagulation management for ECMO. Semin. Cardiothorac. Vasc. Anesth. 2009, 13, 154–175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maier, C.L.; Connors, J.M.; Levy, J.H. Troubleshooting heparin resistance. Hematology 2024, 2024, 186–191. [Google Scholar] [CrossRef] [Scilit]
- Baird, C.W.; Zurakowski, D.; Robinson, B.; Gandhi, S.; Burdis-Koch, L.; Tamblyn, J.; Munoz, R.; Fortich, K.; Pigula, F.A. Anticoagulation and pediatric extracorporeal membrane oxygenation: Impact of activated clotting time and heparin dose on survival. Ann. Thorac. Surg. 2007, 83, 912–919; discussion 919–920. [Google Scholar] [CrossRef] [Scilit]
- Tacquard, C.; Iba, T.; Levy, J.H. Perioperative Anaphylaxis. Anesthesiology 2023, 138, 100–110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hirsh, J.; Guyatt, G.; Albers, G.W.; Harrington, R.; Schünemann, H.J. Antithrombotic and thrombolytic therapy: American College of Chest Physicians Evidence-Based Clinical Practice Guidelines (8th Edition). Chest 2008, 133, 110–112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martindale, S.J.; Shayevitz, J.R.; D’Errico, C. The activated coagulation time: Suitability for monitoring heparin effect and neutralization during pediatric cardiac surgery. J. Cardiothorac. Vasc. Anesth. 1996, 10, 458–463. [Google Scholar] [CrossRef] [Scilit]
- Ranucci, M.; Cotza, M.; Isgrò, G.; Carboni, G.; Ballotta, A.; Baryshnikova, E. Surgical Clinical Outcome REsearch (SCORE) Group. Anti-Factor Xa-Based Anticoagulation during Extracorporeal Membrane Oxygenation: Potential Problems and Possible Solutions. Semin. Thromb. Hemost. 2020, 46, 419–427. [Google Scholar] [CrossRef] [Scilit]
- Favaloro, E.J.; Arunachalam, S.; Dean, E. Performance of direct oral anticoagulant (DOAC) testing by hemostasis laboratories: The Australasian/Asia-Pacific experience. Int. J. Lab. Hematol. 2024, 46, 731–740. [Google Scholar] [CrossRef] [Scilit]
- Devreese, K.M.J.; Bertolaccini, M.L.; Branch, D.W.; de Laat, B.; Erkan, D.; Favaloro, E.J.; Pengo, V.; Ortel, T.L.; Wahl, D.; Cohen, H. An update on laboratory detection and interpretation of antiphospholipid antibodies for diagnosis of antiphospholipid syndrome: Guidance from the ISTH-SSC Subcommittee on Lupus Anticoagulant/Antiphospholipid Antibodies. J. Thromb. Haemost. 2025, 23, 731–744. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ELSO. Guidelines for Cardiopulmonary Extracorporeal Life Support Extracorporeal Life Support Organization, Version 1.4; ELSO: Ann Arbor, MI, USA, 2017; Available online: https://www.elso.org/ecmo-resources/elso-ecmo-guidelines.aspx (accessed on 8 February 2026).
- Ng, J.Y.; D’Souza, M.; Hutani, F.; Choi, P. Management of Heparin-Induced Thrombocytopenia: A Contemporary Review. J. Clin. Med. 2024, 13, 4686. [Google Scholar] [CrossRef] [Scilit]
- Martin, A.M.; Polistena, P.; Mahmud, A.; Bettridge, B.; Morling, A.; Chuah, H.; Yong, A.S.M.; Leahy, M.F. Optimal enoxaparin dosing strategies for venous thromboembolism prophylaxis and treatment of high body weight patients. Thromb. Res. 2021, 207, 116–122. [Google Scholar] [CrossRef] [Scilit]
- Dybdahl, D.; Walliser, G.; Pershing, M.; Collins, C.; Robinson, D. Enoxaparin Dosing for Venous Thromboembolism Prophylaxis in Low Body Weight Patients. Clin. Med. Insights: Blood Disord. 2019, 12, 1179545X19863814. [Google Scholar] [CrossRef] [Scilit]
- Knox, H.; Edwin, S.B.; Giuliano, C.; Paxton, R.A. Venous Thromboembolism Prophylaxis in Low Body Weight Critically Ill Patients. J. Intensive Care Med. 2023, 39, 493–498. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abou Safrah, S.I.; Saad, M.O.; Alasmar, M.; Butt, F.A.; Koraysh, S.K. Enoxaparin dosing for venous thromboembolism prophylaxis in hospitalized underweight adult patients: A retrospective cohort study. Thromb. J. 2025, 23, 45. [Google Scholar] [CrossRef] [Scilit]
- Nemeth, A.; Isherwood, M. Safety and Effectiveness of Reduced Dose Versus Standard Dose Enoxaparin Venous Thromboembolism Prophylaxis in Underweight Medically Ill Patients. Hosp. Pharm. 2023, 58, 178–182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anderson, D.R.; Morgano, G.P.; Bennett, C.; Dentali, F.; Francis, C.W.; Garcia, D.A.; Kahn, S.R.; Rahman, M.; Rajasekhar, A.; Rogers, F.B.; et al. American Society of Hematology 2019 guidelines for management of venous thromboembolism: Prevention of venous thromboembolism in surgical hospitalized patients. Blood Adv. 2019, 3, 3898–3944. [Google Scholar] [CrossRef] [Scilit]
- Chilbert, M.R.; Zammit, K.; Ahmed, U.; Devlin, A.; Radparvar, S.; Schuler, A.; Woodruff, A.E. A systematic review of therapeutic enoxaparin dosing in obesity. J. Thromb. Thrombolysis 2024, 57, 587–597. [Google Scholar] [CrossRef] [Scilit]
- Appay, M.; Kharadi, S.; Nanayakkara, S.; Ryu, J.S.; Pasalic, L.; Alffenaar, J.W. Therapeutic Enoxaparin Dosing in Obesity. Ann. Pharmacother. 2025, 59, 262–276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Estes, J.W. Clinical pharmacokinetics of heparin. Clin. Pharmacokinet. 1980, 5, 204–220. [Google Scholar] [CrossRef] [Scilit]
- Hirsh, J.; Raschke, R.; Warkentin, T.E.; Dalen, J.E.; Deykin, D.; Poller, L. Heparin: Mechanism of action, pharmacokinetics, dosing considerations, monitoring, efficacy, and safety. Chest 1995, 108, 258S–275S. [Google Scholar] [CrossRef] [Scilit]
- Barletta, J.F.; DeYoung, J.L.; McAllen, K.; Baker, R.; Pendleton, K. Limitations of a standardized weight-based nomogram for heparin dosing in patients with morbid obesity. Surg. Obes. Relat. Dis. 2008, 4, 748–753. [Google Scholar] [CrossRef] [Scilit]
- Riney, J.N.; Hollands, J.M.; Smith, J.R.; Deal, E.N. Identifying optimal initial infusion rates for unfractionated heparin in morbidly obese patients. Ann. Pharmacother. 2010, 44, 1141–1151. [Google Scholar] [CrossRef] [Scilit]
- Shlensky, J.A.; Thurber, K.M.; O’Meara, J.G.; Ou, N.N.; Osborn, J.L.; Dierkhising, R.A.; Mara, K.C.; Bierle, D.M.; Daniels, P.R. Unfractionated heparin infusion for treatment of venous thromboembolism based on actual body weight without dose capping. Vasc. Med. 2020, 25, 47–54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- George, C.; Barras, M.; Coombes, J.; Winckel, K. Unfractionated heparin dosing in obese patients. Int. J. Clin. Pharm. 2020, 42, 462–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, K.; Murray, B.; Campbell-Bright, S.; Jones, L.A.; Fabricio Donahue, J.; Nguyen, Q.; Kline, T.M. Adjusted Versus Total Body Weight Dosing for Intravenous Heparin Infusions and Target Attainment in Obese Patients. Hosp. Pharm. 2025, 60, 601–607. [Google Scholar] [CrossRef] [Scilit]
- Flanagan, T.; Sharma, M.; Cao, U.T.; Wang, X.; Kataria, V. Evaluation of unfractionated heparin dosing using an antifactor-Xa-based protocol in non-obese vs. obese patients for acute venous thromboembolism. J. Thromb. Thrombolysis 2025, 58, 556–565. [Google Scholar] [CrossRef] [Scilit]
- Weitz, J.I. Low-molecular-weight heparins. N. Engl. J. Med. 1997, 337, 688–698. [Google Scholar] [CrossRef] [Scilit]
- Eck, R.J.; Bult, W.; Wetterslev, J.; Gans, R.O.B.; Meijer, K.; van der Horst, I.C.C.; Keus, F. Low Dose Low-Molecular-Weight Heparin for Thrombosis Prophylaxis: Systematic Review with Meta-Analysis and Trial Sequential Analysis. J. Clin. Med. 2019, 8, 2039. [Google Scholar] [CrossRef] [Scilit]
- Placella, G.; Pace, V.; Antinolfi, P.; Salini, V. A Review of The Current Literature on LMWH Administered at Different Times in Relation to MOS (Major Orthopaedic Surgery): Assessment of The Safety and Efficacy of The Different Proposed Strategies. Br. J. Surg. 2021, 108, znab134.190. [Google Scholar] [CrossRef] [Scilit]
- Zhu, L.; Zhu, B.; Bing, P.; Qi, M.; He, B. Effectiveness and safety of rivaroxaban or low-molecular-weight heparin in non-major orthopedic surgery: A meta-analysis of randomized controlled trials. J. Orthop. Surg. Res. 2024, 19, 609. [Google Scholar] [CrossRef] [Scilit]
- Levy, J.H.; Connors, J.M. Heparin Resistance—Clinical Perspectives and Management Strategies. N. Engl. J. Med. 2021, 385, 826–832. [Google Scholar] [CrossRef] [Scilit]
- Bolliger, D.; Erdoes, G.; Mauermann, E. Heparin Resistance: Definition, Risk Factors, and Therapeutic Approaches. J. Cardiothorac. Vasc. Anesth. 2025, 39, 2293–2295. [Google Scholar] [CrossRef] [Scilit]
- Staples, M.H.; Dunton, R.F.; Karlson, K.J.; Leonardi, H.K.; Berger, R.L. Heparin resistance after preoperative heparin therapy or intraaortic balloon pumping. Ann. Thorac. Surg. 1994, 57, 1211–1216. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.; Phoon, P.H.Y.; Hwang, N.C. Heparin Resistance During Cardiopulmonary Bypass in Adult Cardiac Surgery. J. Cardiothorac. Vasc. Anesth. 2022, 36, 4150–4160. [Google Scholar] [CrossRef] [Scilit]
- Smythe, M.A.; Priziola, J.; Dobesh, P.P.; Wirth, D.; Cuker, A.; Wittkowsky, A.K. Guidance for the practical management of the heparin anticoagulants in the treatment of venous thromboembolism. J. Thromb. Thrombolysis. 2016, 41, 165–186. [Google Scholar] [CrossRef] [Scilit]
- Levy, J.H.; Connors, J.M. Andexanet alfa use in cardiac surgical patients: A Xa inhibitor and heparin reversal agent. J. Cardiothorac. Vasc. Anesth. 2021, 35, 265–266. [Google Scholar] [CrossRef] [Scilit]
- Weiss, R.J.; Esko, J.D.; Tor, Y. Targeting heparin and heparan sulfate protein interactions. Org. Biomol. Chem. 2017, 15, 5656–5668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lane, D.A.; Pejler, G.; Flynn, A.M.; Thompson, E.A.; Lindahl, U. Neutralization of heparin-related saccharides by histidine-rich glycoprotein and platelet factor 4. J. Biol. Chem. 1986, 261, 3980–3986. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.F.; Makar, R.S.; Antic, D.; Levy, J.H.; Douketis, J.D.; Connors, J.M.; Carrier, M.; Zwicker, J.I. Management of hemostatic complications in acute leukemia: Guidance from the SSC of the ISTH. J. Thromb. Haemost. 2020, 18, 3174–3183. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Konkle, B.A.; Bauer, K.A.; Weinstein, R.; Greist, A.; Holmes, H.E.; Bonfiglio, J. Use of recombinant human antithrombin in patients with congenital antithrombin deficiency undergoing surgical procedures. Transfusion 2003, 43, 390–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Minami, K.; Kumagai, K.; Sugai, Y.; Nakamura, K.; Naito, S.; Oshima, S. Efficacy of Oral Factor Xa Inhibitor for Venous Thromboembolism in a Patient with Antithrombin Deficiency. Intern. Med. 2018, 57, 2025–2028. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levy, J.H.; Douketis, J.; Weitz, J.I. Reversal agents for non-vitamin K antagonist oral anticoagulants. Nat. Rev. Cardiol. 2018, 15, 273–281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nicolas, D.; Nicolas, S.; Hodgens, A.; Reed, M. Heparin-Induced Thrombocytopenia. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2025. Available online: https://www.ncbi.nlm.nih.gov/books/NBK482330/ (accessed on 7 March 2026).
- Joseph, J.; Rabbolini, D.; Enjeti, A.K.; Favaloro, E.; Kopp, M.C.; McRae, S.; Pasalic, L.; Chee Wee, T.; Ward, C.M.; Chong, B.H. Diagnosis and management of heparin-induced thrombocytopenia: A consensus statement from the Thrombosis and Haemostasis Society of Australia and New Zealand HIT Writing Group. Med. J. Aust. 2019, 210, 509–516. [Google Scholar] [CrossRef] [Scilit]
- Crowther, M.A.; Cook, D.J.; Albert, M.; Williamson, D.; Meade, M.; Granton, J.; Skrobik, Y.; Lange-vin, S.; Mehta, S.; Hebert, P.; et al. The 4Ts scoring system for heparin-induced thrombocytopenia in medical-surgical intensive care unit patients. J. Crit. Care 2010, 25, 287–293. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- May, J.; Cuker, A. Practical guide to the diagnosis and management of heparin-induced thrombocytopenia. Hematol. Am. Soc. Hematol. Educ. Program. 2024, 2024, 388–395. [Google Scholar] [CrossRef] [Scilit]
- Bakchoul, T. An update on heparin-induced thrombocytopenia: Diagnosis and management. Expert. Opin. Drug Saf. 2016, 15, 787–797. [Google Scholar] [CrossRef] [Scilit]
- Aljumaa, R.M.; Dabaliz, A.; Sabur, H.; Mushtaq, A.; Aljumaa, M.M.; Tamim, H.; Owaidah, T.; Sajid, M.R. Inter-Observer Agreement and Laboratory Correlation of the 4T Scoring Model for Heparin-Induced Thrombocytopenia: A Single-Center Retrospective Study and Literature Review. J. Clin. Med. 2025, 14, 8692. [Google Scholar] [CrossRef] [Scilit]
- Larsen, E.L.; Nilius, H.; Studt, J.D.; Tsakiris, D.A.; Greinacher, A.; Mendez, A.; Schmidt, A.; Wuillemin, W.A.; Gerber, B.; Vishnu, P.; et al. Accuracy of Diagnosing Heparin-Induced Thrombocytopenia. JAMA Netw. Open. 2024, 7, e243786. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Minet, V.; Dogné, J.M.; Mullier, F. Functional Assays in the Diagnosis of Heparin-Induced Thrombocytopenia: A Review. Molecules 2017, 22, 617. [Google Scholar] [CrossRef] [Scilit]
- Warkentin, T.E. How I diagnose and manage HIT. Hematol. ASH Educ. Program 2011, 1, 143–149. [Google Scholar] [CrossRef] [Scilit]
- Nagler, M.; Bachmann, L.M.; Ten Cate, H.; Ten Cate-Hoek, A. Diagnostic value of immunoassays for heparin-induced thrombocytopenia: A systematic review and meta-analysis. Blood 2015, 127, 546–557. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brodard, J.; Alberio, L.; Angelillo-Scherrer, A.; Nagler, M. Accuracy of heparin-induced platelet aggregation test for the diagnosis of heparin-induced thrombocytopenia. Thromb. Res. 2020, 185, 27–30. [Google Scholar] [CrossRef] [Scilit]
- Bakchoul, T.; Zollner, H.; Greinacher, A. Current insights into the laboratory diagnosis of HIT. Int. J. Lab. Hematol. 2014, 36, 296–305. [Google Scholar] [CrossRef] [Scilit]
- Boer, C.; Meesters, M.I.; Veerhoek, D.; Vonk, A.B.A. Anticoagulant and side-effects of protamine in cardiac surgery: A narrative review. Br. J. Anaesth. 2018, 120, 914–927. [Google Scholar] [CrossRef] [Scilit]
- Chargaff, E.; Olson, K.B. Studies on the chemistry of blood coagulation: VI. Studies on the action of heparin and other anticoagulants. The influence of protamine on the anticoagulant effect in vivo. J. Biol. Chem. 1937, 122, 153–167. [Google Scholar] [CrossRef] [Scilit]
- Portmann, A.F.; Holden, W.D. Protamine sulphate, heparin, and blood coagulation. J. Clin. Investig. 1949, 28, 1451–1458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levy, J.H.; Ghadimi, K.; Kizhakkedathu, J.N.; Iba, T. What’s fishy about protamine? Clinical use, adverse reactions, and potential alternatives. J. Thromb. Haemost. 2023, 21, 1714–1723. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yongyukantorn, K.; Rujirojindakul, P.; Karnjanawanichkul, O. Optimal Dose of Protamine for Heparin Reversal in Patients Undergoing Cardiopulmonary Bypass Surgery. J. Med. Assoc. Thai 2018, 101, 1037–1041. [Google Scholar]
- Goedhart, A.L.M.; Gerritse, B.M.; Rettig, T.C.D.; van Geldorp, M.W.A.; Bramer, S.; van der Meer, N.J.M.; Boonman-de Winter, L.J.; Scohy, T.V. A 0.6-protamine/heparin ratio in cardiac surgery is associated with decreased transfusion of blood products. Interact. Cardiovasc. Thorac. Surg. 2020, 31, 391–397. [Google Scholar] [CrossRef] [Scilit]
- Balbaa, E.; Gadelmawla, A.F.; Tawfik, A.M.; Naeem, A.; Elbataa, A.; Bazzazeh, M.; Fatiem, A.R.; Ali, K.; Altobaishat, O.; Abuelazm, M. Protamine sulphate for heparin reversal in percutaneous cardiac interventions: A systematic review and meta-analysis of randomized controlled trials. Naunyn-Schmiedeberg’s Arch. Pharmacol. 2025, 398, 16507–16520. [Google Scholar] [CrossRef] [Scilit]
- Teoh, K.H.; Young, E.; Blackall, M.H.; Roberts, R.S.; Hirsh, J. Can extra protamine eliminate heparin rebound following cardiopulmonary bypass surgery? J. Thorac. Cardiovasc. Surg. 2004, 128, 211–219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peeters, M.; Yilmaz, A.; Vandekerkhof, J.; Kaya, A. Protamine Induced Anaphylactic Shock after Peripheral Vascular Surgery. Ann. Vasc. Surg. 2020, 69, 450.e13–450.e15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mochizuki, T.; Olson, P.J.; Szlam, F.; Ramsay, J.G.; Levy, J.H. Protamine reversal of heparin affects platelet aggregation and activated clotting time after cardiopulmonary bypass. Anesth. Analg. 1998, 87, 781–785. [Google Scholar] [CrossRef] [Scilit]
- Schroeder, M.; Hogwood, J.; Gray, E.; Mulloy, B.; Hackett, A.M.; Johansen, K.B. Protamine neutralisation of low molecular weight heparins and their oligosaccharide components. Anal. Bioanal. Chem. 2011, 399, 763–771. [Google Scholar] [CrossRef] [Scilit]
- Crowther, M.A.; Petr, K.; Peng, L.; Frank, C.; Leslie, B.B.; Anthony, C.K.C. Significant Differences in Neutralization of Heparin and Its Low Molecular Fragments by Protamine Sulfate: An In Vivo Study. Blood 2004, 104, 1850. [Google Scholar] [CrossRef] [Scilit]
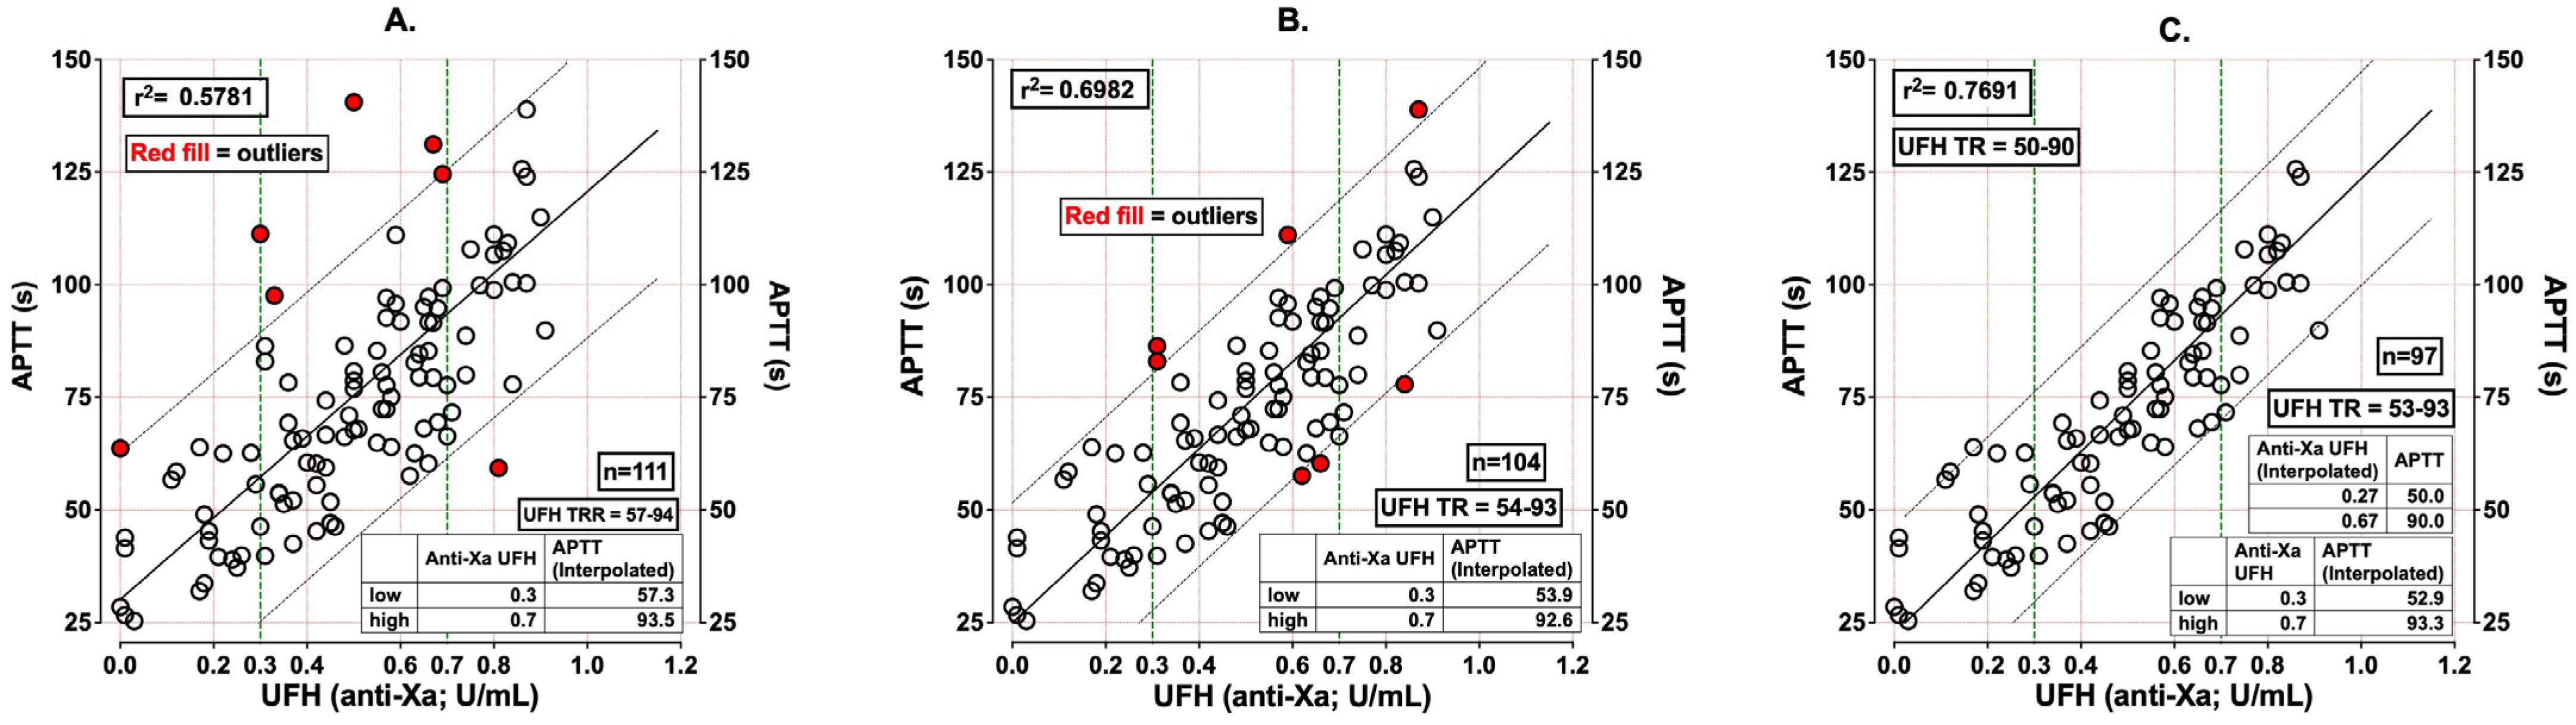

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.