


Abstract
(1) Background: Zinc is an essential micronutrient involved in immune regulation, epithelial barrier integrity, and the host response to bacterial infections. However, the clinical benefits of zinc supplementation across different age groups remain uncertain, with heterogeneous findings and variable dosing strategies reported in the literature. (2) Objectives: To map and summarize randomized controlled trials (RCTs) evaluating zinc supplementation (either as treatment or prophylaxis) for bacterial infection outcomes in neonates, children, and adults, and to identify gaps requiring further research, including the use of zinc-based nanoparticles. (3) Eligibility Criteria: We included English-language RCTs that evaluated zinc supplementation and reported clinical outcomes related to bacterial infections. Observational studies, trials without infection-related outcomes, and studies not involving human participants were excluded. (4) Sources of Evidence: A MEDLINE (PubMed) search was conducted from 2000 to 1 November 2025 using predefined keywords related to zinc supplementation, neonates, children, adults, and bacterial infections. Reference lists of eligible articles were screened to identify additional studies. (5) Charting Methods: Data were charted for each included study, including population characteristics, zinc dosing and regimen, type of supplementation (therapeutic or prophylactic), main infection-related outcomes, and key findings. Data charting was performed independently and verified within the research team. (6) Results: A total of 51 RCTs were included: 10 in neonates, 32 in children, and 9 in adults. In neonates, therapeutic zinc supplementation as an adjunct to antibiotics showed heterogeneous results, with some studies reporting reductions in morbidity, inflammatory markers or mortality, while others found no significant differences in clinical outcomes. In children, zinc supplementation consistently reduced the duration and severity of diarrheal episodes and, in several trials, improved the resolution of respiratory infections. In adults, the evidence was limited but suggested potential benefits in selected populations, such as burn patients or those with zinc deficiency or immunologic dysfunction. Variability in zinc dosage, treatment duration, and outcome definitions limits direct comparison across studies. (7) Conclusions: Zinc supplementation appears to provide benefits in neonates and children, whereas evidence in adults remains mixed and inconclusive. Standardized, well-powered RCTs are needed to define optimal dosing strategies, identify populations most likely to benefit, and clarify the mechanisms underlying zinc’s anti-infective effects. Future research should consider the use of zinc oxide nanoparticles (ZnO-NPs) demonstrated broad-spectrum antimicrobial activity and potential synergy with antibiotics, although clinical data remain still limited.
1. Introduction
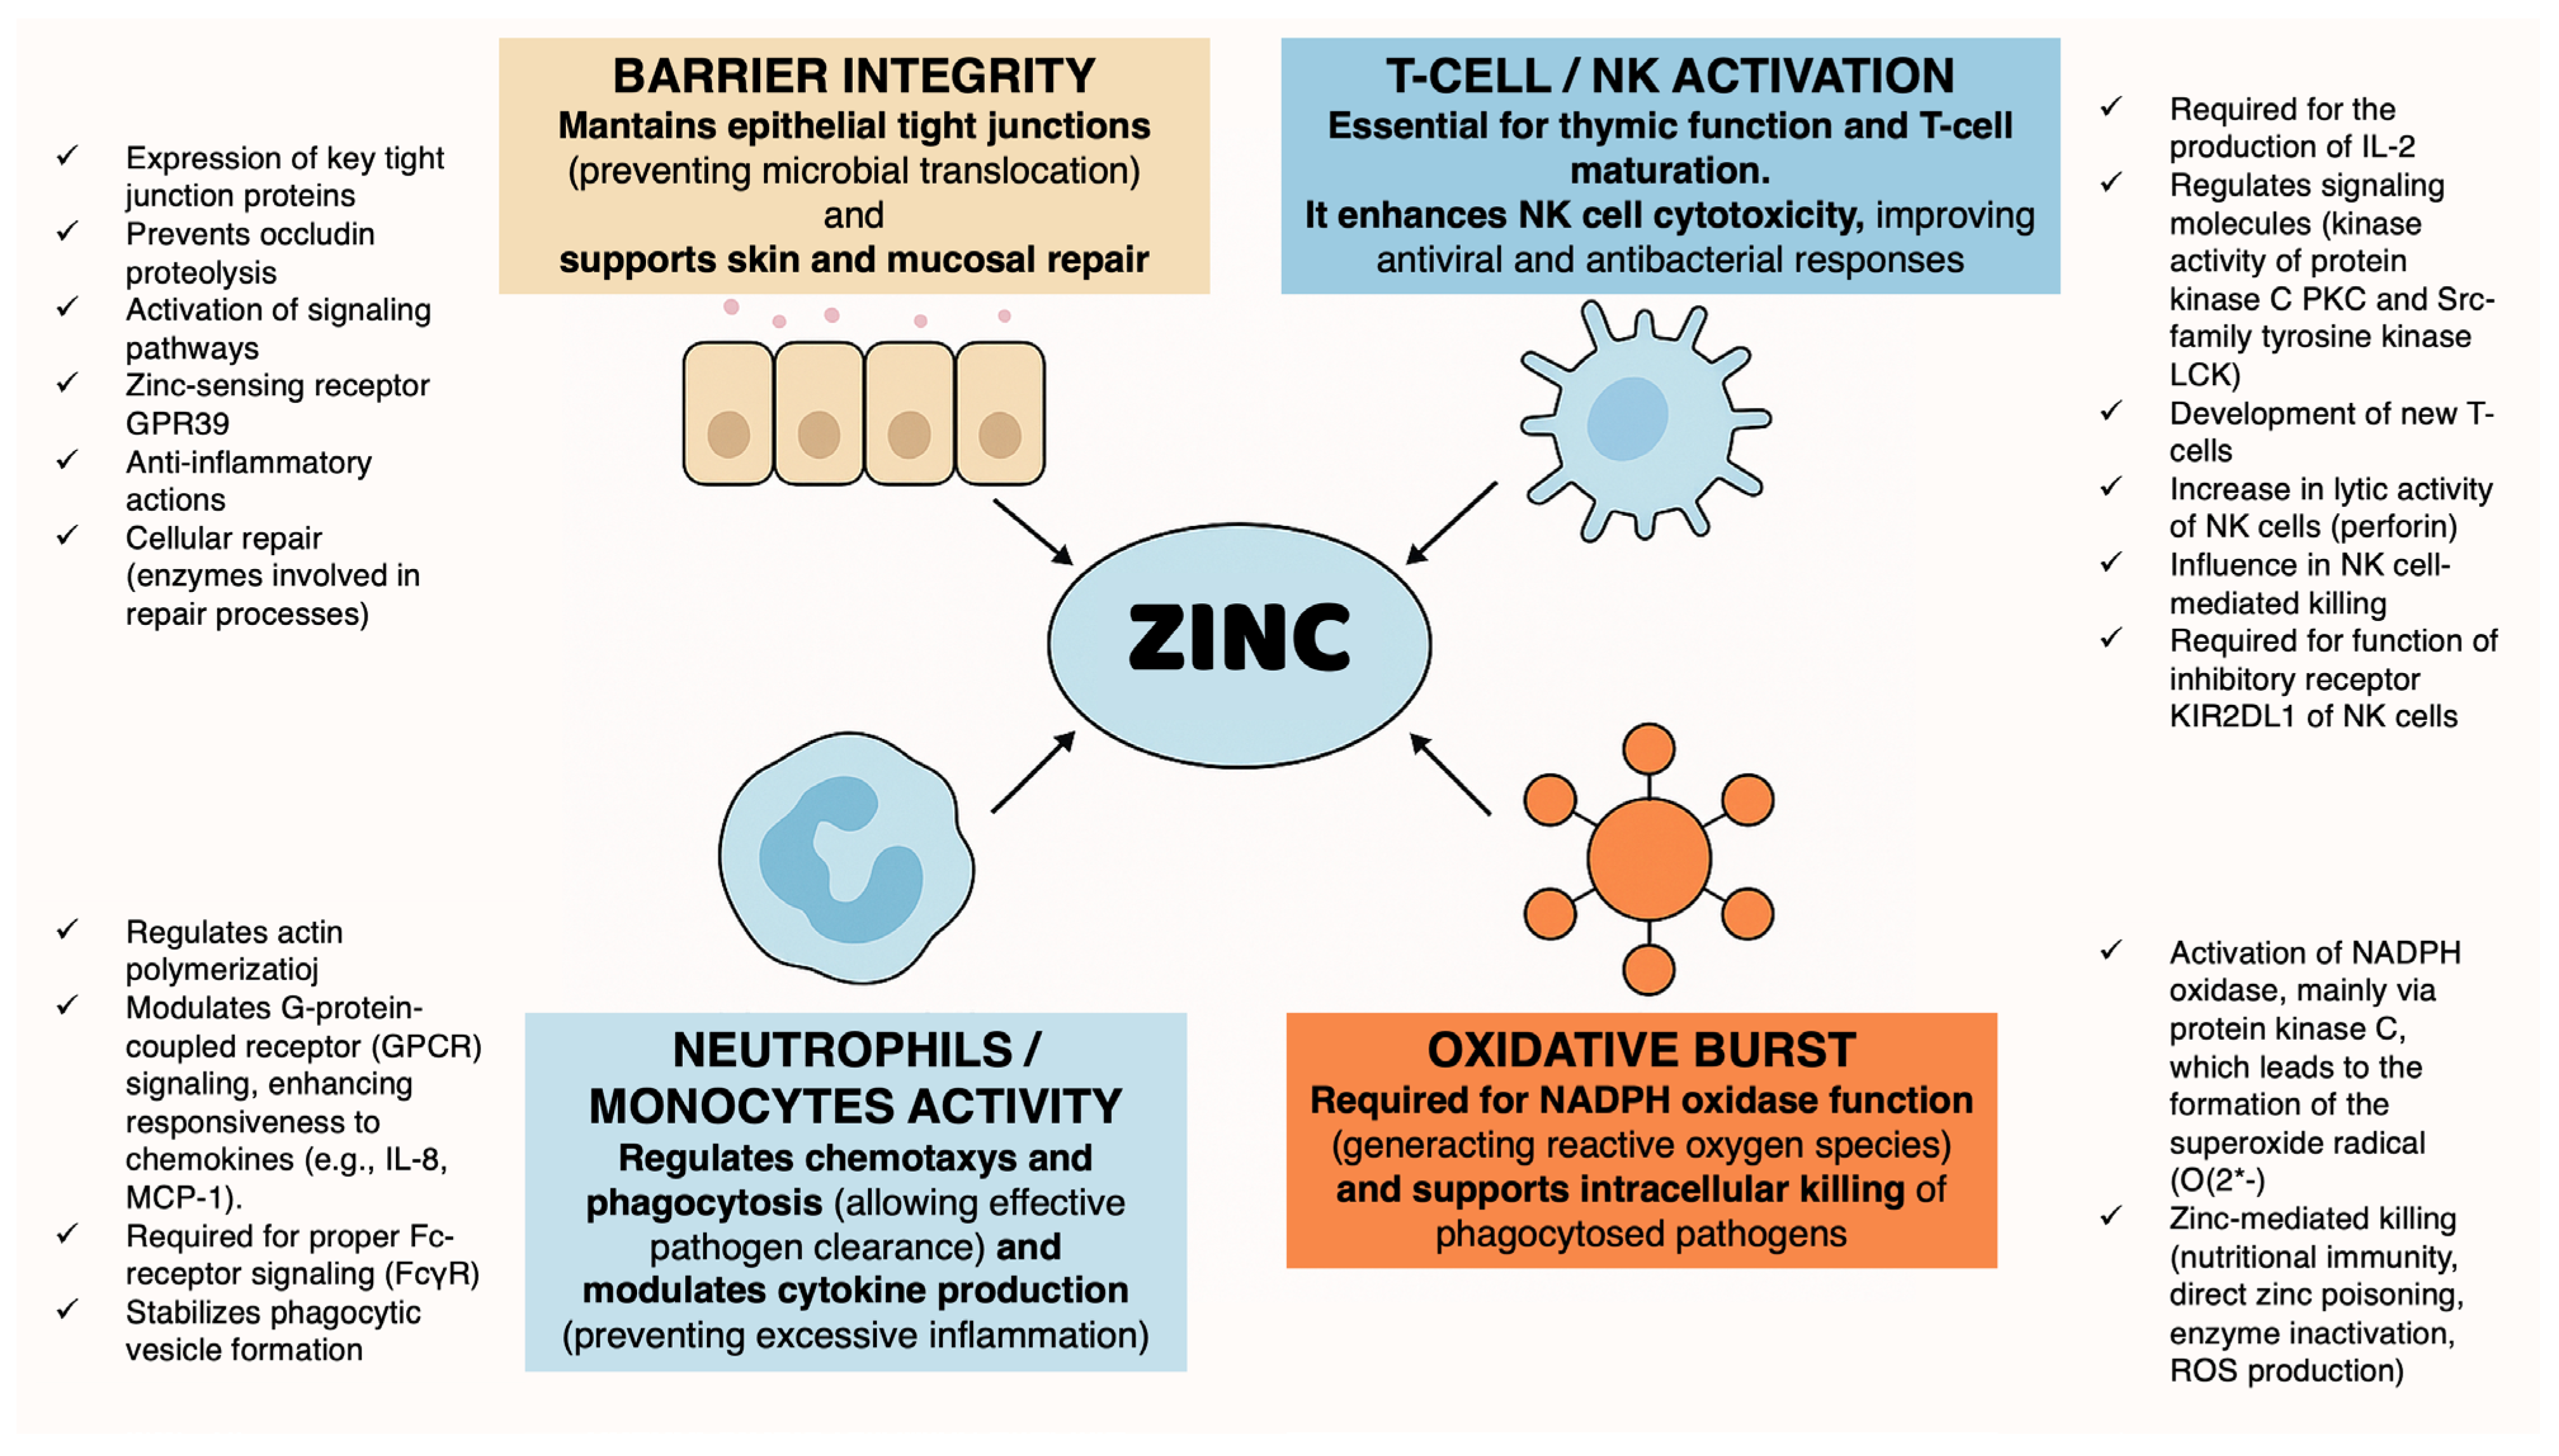
Zinc is a key element for numerous enzymes and transcription factors, and zinc deficiency is associated with major clinical consequences, including growth retardation, impaired cell-mediated immunity, and cognitive impairment [1]. Zinc deficiency remains a major global health problem, affecting approximately 17% of the world’s population, with the highest burden in low- and middle-income countries. Among children under five years of age, the estimated prevalence ranges from 20% to over 30% depending on geographic region and dietary patterns [2]. Acquired zinc deficiency is characterized by clinical features such as diarrhea, recurrent infections, and skin lesions [3]. Zinc plays a central role in immune function, epithelial integrity, and inflammatory modulation (Figure 1) [4,5,6,7,8]; consequently, zinc deficiency has been associated with increased susceptibility to respiratory infections, diarrhea, and impaired host defense. Current epidemiological data highlight the clinical relevance of understanding zinc status in relation to infection risk and treatment outcomes [9].
Figure 1.
Schematic representation of the key immunological functions supported by zinc.
Beyond its essential role in host immune defense, zinc is also a critical micronutrient for bacterial physiology, as it is required for the activity of multiple bacterial enzymes and regulatory systems. During infection, the host actively modulates zinc availability as part of nutritional immunity, while pathogens have evolved mechanisms to acquire zinc under restrictive conditions. This dual role at the host–pathogen interface makes zinc supplementation a biologically plausible intervention to modulate infection outcomes, particularly in populations at higher risk of zinc deficiency such as neonates, children, and vulnerable adult groups. During infections, total plasma zinc levels decrease in order to restrict bacterial access to zinc. This process is mainly mediated by the upregulation of the zinc transporter ZIP14 through an interleukin-6–mediated pathway. This response occurs rapidly (within a few hours), resulting in reduced plasma zinc levels and concomitant zinc accumulation in the liver [10,11].
Different bacterial species have developed specific strategies to overcome zinc limitation. For example, Neisseria species (N. gonorrhoeae and N. meningitidis) express dedicated zinc import systems, including ZnuC, ZnuB, and ZnuA. Znu-like systems were also found in various bacteria, including E. coli and K. pneumoniae [11].
Randomized controlled trials (RCTs) evaluating zinc supplementation have been conducted in neonates, children, and adults, but differ widely in population characteristics, dosing regimens, clinical settings, and infection-related outcomes. This variability has resulted in fragmented evidence and challenges in drawing generalizable conclusions.
Zinc requirements, baseline deficiency prevalence, immune system maturation, and infection outcomes vary substantially across the life course. Neonates and young children are particularly vulnerable to zinc deficiency and infectious morbidity, whereas adults may exhibit heterogeneous responses depending on nutritional status, comorbidities, and immune dysfunction. For this reason, a unified but age-stratified analysis is required to comprehensively evaluate the effects of zinc supplementation on bacterial infections across different stages of life.
This scoping review aimed to systematically map randomized controlled trials evaluating zinc supplementation for bacterial infection outcomes in neonates, children, and adults. By synthesizing age-stratified evidence, we sought to identify consistent effects, sources of heterogeneity, and knowledge gaps, including emerging research directions related to antimicrobial resistance and zinc-based nanotechnologies.
2. Results
2.1. Study Description
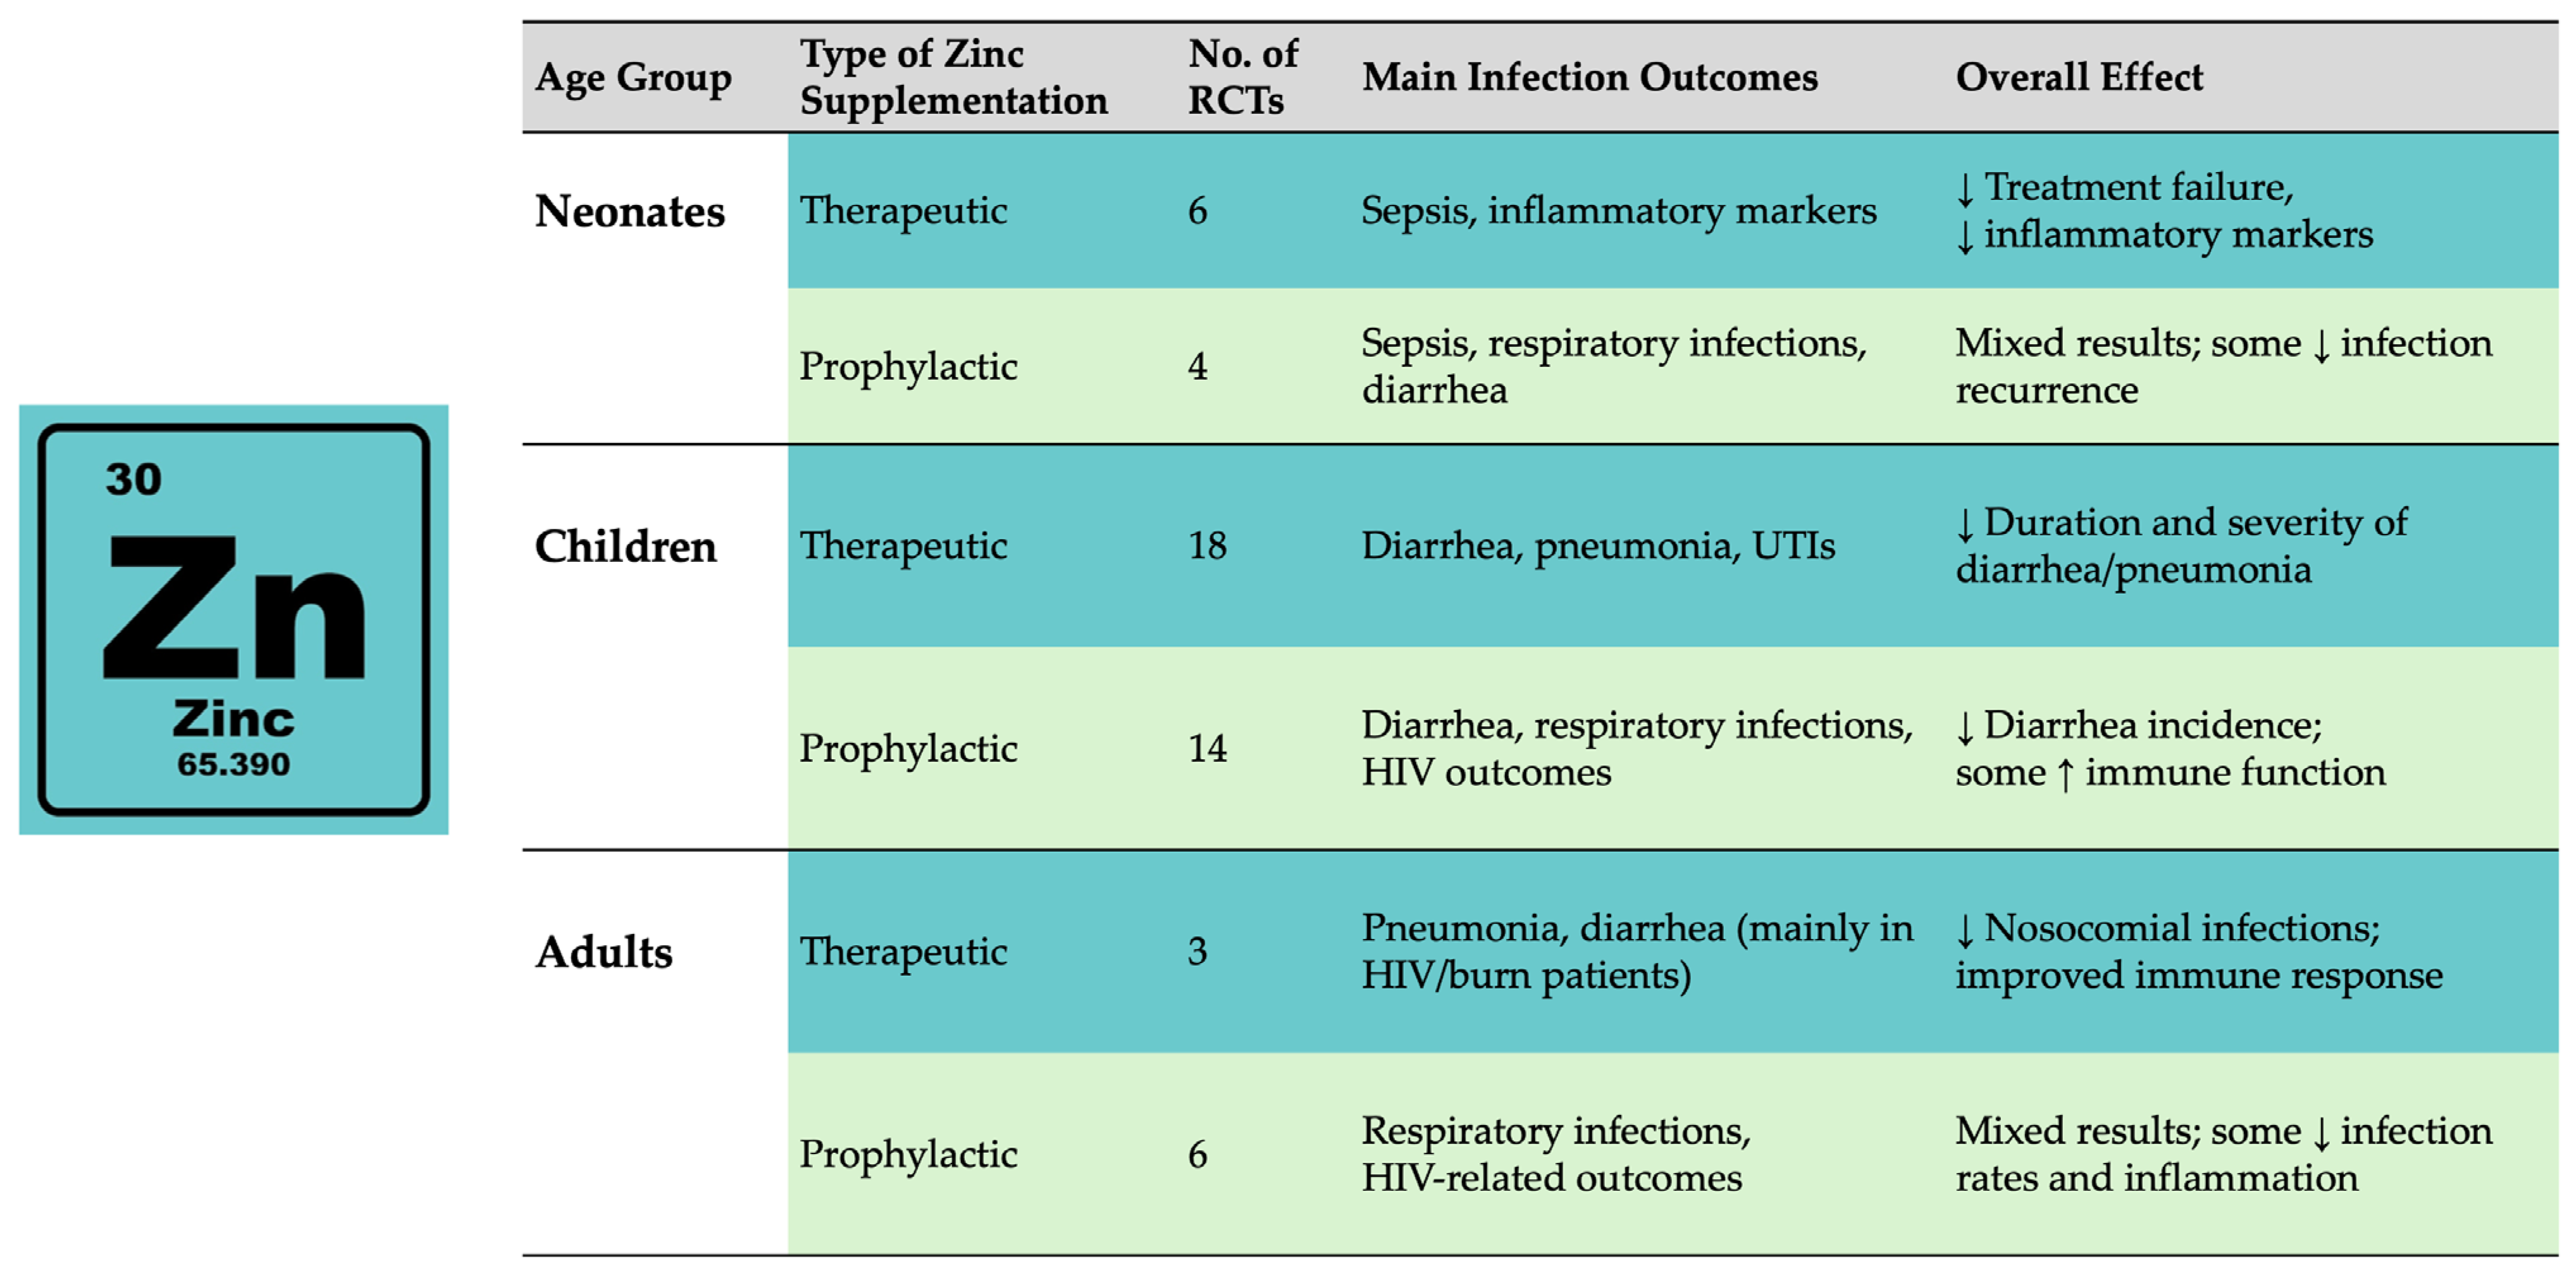
After the research process using the described terms and a manual search of additional references, 51 Randomized Controlled Trials (RCTs) were included in our review: 27 for therapeutic zinc supplementation and 24 for prophylactic zinc supplementation (Figure 2).
Figure 2.
Summary of the current evidence about the relationship between zinc supplementation and infection, showing the age group, type of zinc supplementation, the number of included RCTs, main infection outcomes, and overall effect. Arrows indicate the direction of change over time (↑ increase; ↓ decrease).
2.2. Zinc Supplementation Against Infections in Neonates and Children
The effect of zinc differs substantially between therapeutic and preventive RCTs, with therapeutic supplementation showing the clearest benefits in septic neonates and preventive strategies demonstrating more heterogeneous results depending on baseline zinc status and population risk.
Table 1 describes the main RCTs on therapeutic and prophylactic zinc supplementation in neonates to date [12,13,14,15,16,17,18,19,20,21].
Table 1.
Main RCTs on zinc supplementation reporting clinical outcomes about bacterial infections in neonatal age. Arrows indicate the direction of change over time (↑ increase; ↓ decrease).
Irfan et al. summarized this evidence in a meta-analysis: therapeutic zinc supplementation during sepsis may significantly reduce treatment failure and potentially reduce the mortality rate [22]. Conversely, further randomized controlled trials are needed to support prophylactic zinc supplementation for preventing sepsis, given the different doses used [18,19].
Table 2 describes the main RCTs on therapeutic and prophylactic zinc supplementation in children to date [23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54]. There were no studies about therapeutic zinc supplementation in sepsis. Most studies aimed to evaluate the effects of therapeutic zinc supplementation in children with diarrhea, with a significant reduction in the episode’s duration or an increased immune response [23,24,25,26,28,30,31,32,33,36,40].
Table 2.
Main RCTs on zinc supplementation reporting clinical outcomes about bacterial infections in children. Arrows indicate the direction of change over time (↑ increase; ↓ decrease).
The aims of the studies about prophylactic zinc supplementation were heterogeneous, from the prevention of diarrhea to the increase in CD4+ cells in HIV-infected children [41,49,51].
2.3. Zinc Supplementation Against Infections in Adults
Table 3 describes the main RCTs on therapeutic and prophylactic zinc supplementation in adults to date [55,56,57,58,59,60,61,62,63]. The aims of the studies concerning therapeutic zinc supplementation were heterogeneous, from the risk of nosocomial pneumonia in patients with large thermal burns to the immune response in HIV-infected adults [55,56,57]. Conversely, the number of CD4+ cells in patients with HIV was the aim of most studies concerning prophylactic supplementation [61,62,63].
Table 3.
Main RCTs on zinc supplementation reporting clinical outcomes about bacterial infections in adults. Arrows indicate the direction of change over time (↑ increase; ↓ decrease).
3. Discussion
An estimated 17% of the world’s population is at risk of insufficient zinc intake [2]. In particular, over half of preschool-aged children worldwide have micronutrient deficiencies, including zinc [64]. Furthermore, Littlejohn et al. showed that multiple micronutrient deficiencies (including zinc) in early life are associated with alterations in the gut microbiome and intrinsic antibiotic resistance genes in mice [65], highlighting micronutrient deficiency as a relevant public health concern. In this scoping review, we provided an integrated overview of RCTs evaluating zinc supplementation for the prevention and treatment of bacterial infections across the life course, from preterm neonates to adults.
3.1. Effects of Zinc Deficiency on Immune Function
Zinc is a key regulator of immune function; therefore, its deficiency can favor the development of a pro-inflammatory phenotype [66].
The maturation and functionality of T and B lymphocytes are negatively impacted by zinc deficiency. A well-known effect of zinc deficiency on T cells is a distorted Th1/Th2 balance, favoring Th2-driven allergic responses [60]. Zinc homeostasis is crucial for T-cell maturation and differentiation, and zinc supplementation may restore this dysfunction [60,67].
Older adults have been shown to exhibit dysfunctional adaptive immunity, characterized by pathologically increased interleukin-6 release, diminished T-cell activation, and reduced responses to stimulation or immunization [60,68,69].
Innate immunity can also be impaired by zinc deficiency, with negative effects on neutrophil functions (phagocytosis, oxidative burst, degranulation, cytokine production) [70] and natural killer (NK) cell function (decreased recognition of major histocompatibility complex class I on target cells with reduced zinc levels, as well as inhibitory killer-cell Ig-like receptor—KIR—polymerization in the presence of zinc) [66,71].
3.2. Zinc Supplementation Against Infections in Neonates and Children
The strongest and most consistent evidence for the anti-infective effects of zinc supplementation emerges in early life, when both zinc deficiency and infectious morbidity are highly prevalent. Combining 28 randomized controlled trials (including 237,068 participants), a meta-analysis revealed that zinc supplementation in children under 5 years significantly reduced the risk of all-cause mortality by 44%. Considering only low birth weight (LBW) infants, zinc supplementation reduced all-cause mortality by 52% [72].
From the first days of life, zinc appears to play a crucial role in defense against bacterial infections. Indeed, zinc deficiency has been demonstrated in neonates (especially if born preterm) and has been related to a higher infectious risk [73].
Available therapeutic RCTs in neonates showed that zinc supplementation supports the resolution of sepsis and improves outcomes. Overall, seven studies (70%) evaluating zinc supplementation reported beneficial effects, while three (30%) did not (Figure 3).
Figure 3.
Summary of the current evidence from RCTs on zinc supplementation in neonates.
In older children, most studies evaluated the effects of therapeutic zinc supplementation in diarrhea, with a significant reduction in the episode’s duration or an increased immune response [23,24,25,26,28,30,31,32,33,36,40].
Moreover, a Cochrane review evidenced that the incidence of acute lower respiratory infections in children aged 2 months to 59 months was reduced by 35% (RR: 0.65, 95% CI: 0.52–0.82) with additional zinc intakes of less than 20 mg per day. More precisely, among the children who received zinc supplements, the incidence and prevalence of pneumonia were 13% (RR: 0.87, 95% CI: 0.81–0.94) and 41% (RR: 0.59, 95% CI: 0.35–0.99) lower, respectively [74].
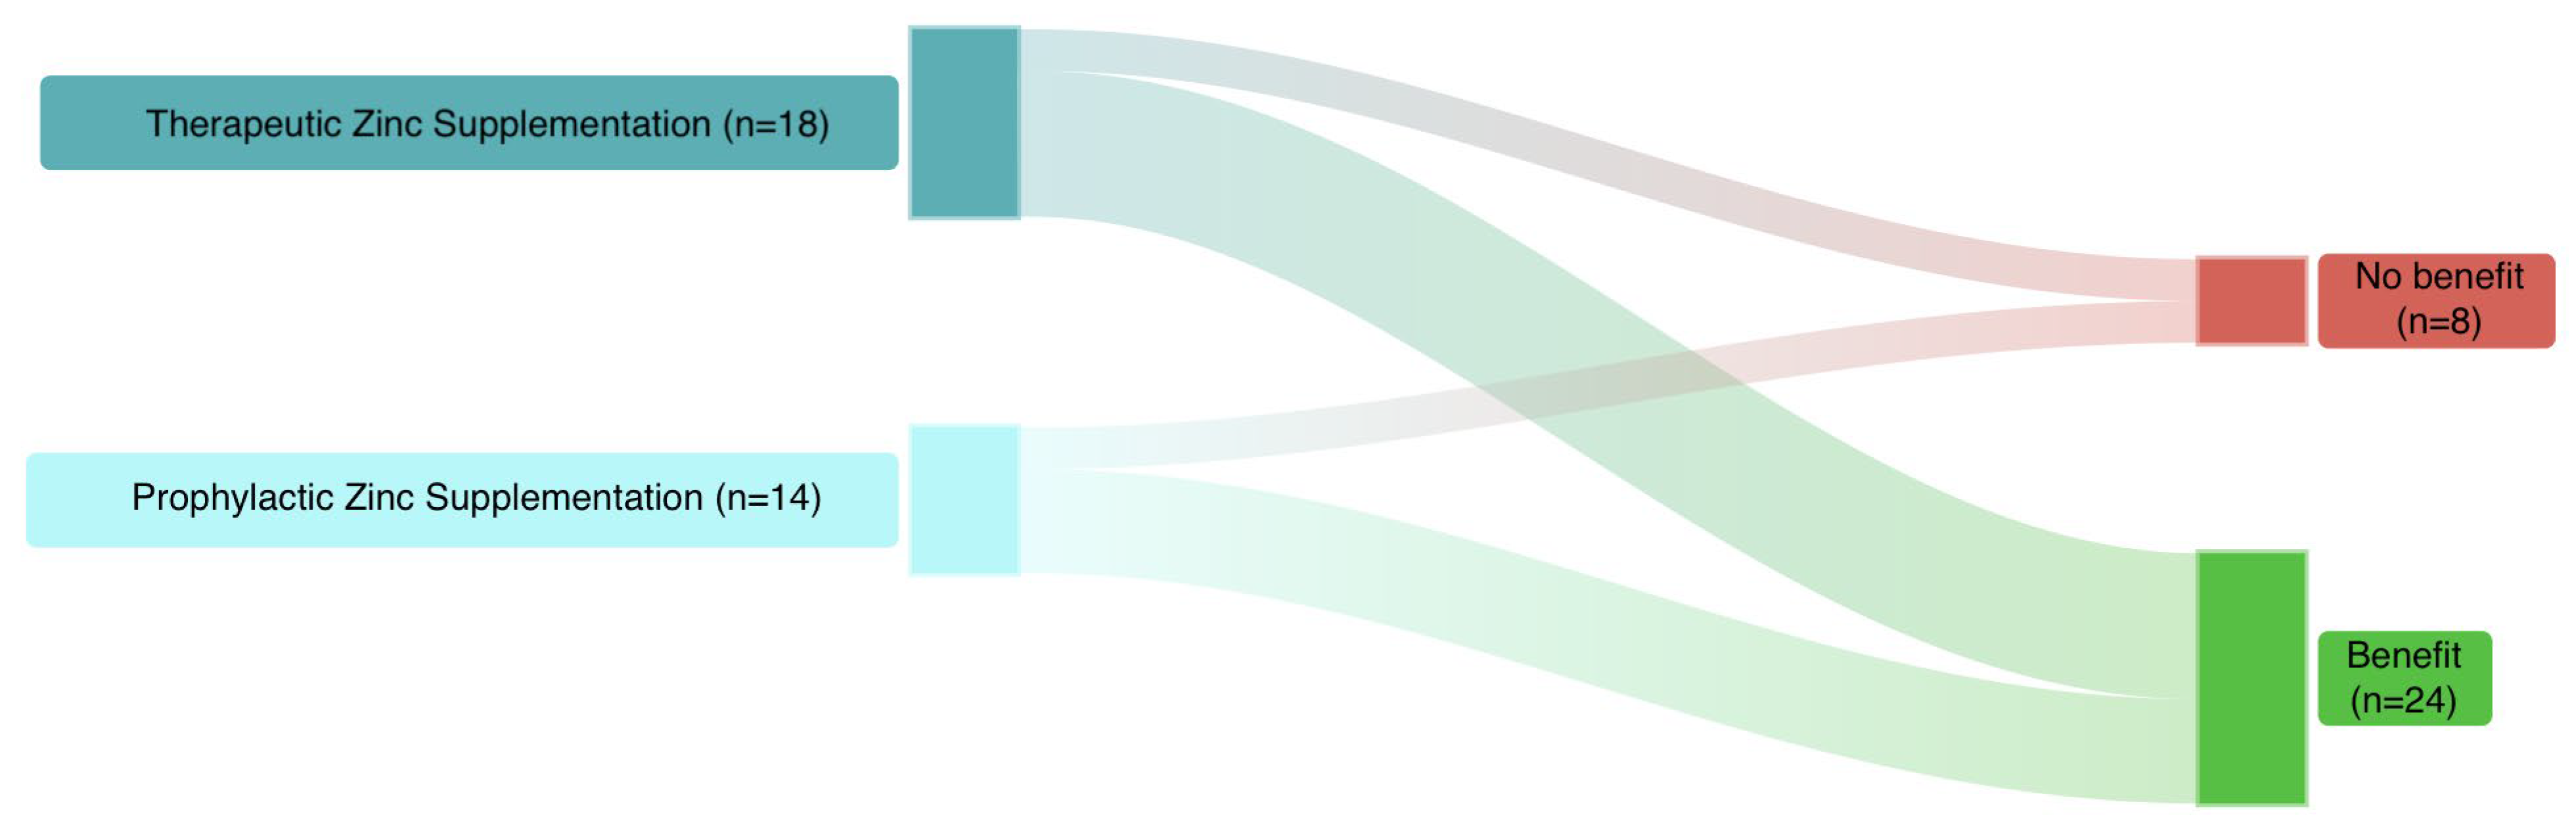
From available RCTs in children, twenty-four studies (75%) reported some benefits, while eight (25%) did not (Figure 4).
Figure 4.
Summary of the current evidence from RCTs on zinc supplementation in children.
3.3. Zinc Supplementation Against Infections in Adults
Among adults, especially those with critical illness, HIV infection, or burn injuries, zinc supplementation has been associated with reduced nosocomial infections and improved immunological recovery, although findings remain heterogeneous across settings [55,56,57,58,60,62,63].
Furthermore, beyond available RCTs in the literature, which we previously summarized, several non-randomized studies also reported a potential role of zinc supplementation in preventing infections in adults. A better specific immune response has been identified in patients undergoing therapeutic zinc supplementation, in particular when zinc levels were low [55,56,57].
Lotfi et al. reported that end-stage renal disease patients on hemodialysis had lower serum zinc levels, which were associated with an increased risk of bacterial infection (although results were unadjusted for other covariates), compared to non-infected patients and healthy individuals. Catheter site infections and urinary tract infections were the most common infections [75].
Being one of the main causes of hospitalization and mortality for older people, particularly for those residing in nursing homes, pneumonia is a serious public health concern. In a prior clinical investigation, Meydani et al. showed that, compared to those with appropriate serum zinc levels, 29% of nursing home residents had low serum zinc levels (<70 mg/dL), which coincided with a two-fold increase in pneumonia incidence and duration, and increased antibiotic use, and overall mortality [76]. Ortega et al. are conducting a randomized, placebo-controlled, double-blind clinical pilot trial about zinc supplementation in the elderly to prevent pneumonia (NCT05527899). The results of this study will provide new insights concerning the safety and efficacy of zinc supplementation (30 and 60 mg/day elemental zinc), as well as the correlation between serum and cellular zinc concentrations [77].
Finally, Kiabi et al. found that zinc supplementation might be associated with a significant reduction in ventilator-associated pneumonia in adult mechanically ventilated trauma patients [78].
Summarizing the few available RCTs in adults, seven studies (77.8%) reported some benefits, while two (22.2%) did not (Figure 5).
Figure 5.
Summary of the current evidence from RCTs on zinc supplementation in adults.
Across the included RCTs, zinc was administered in different formulations, including inorganic and organic salts. However, most trials did not directly compare different zinc forms, and dosing was primarily based on elemental zinc content. Therefore, for the purposes of this scoping review, zinc formulations were considered equivalent with respect to clinical support, as available evidence does not allow for definitive conclusions regarding differential bioavailability or efficacy on infection outcomes.
3.4. Zinc and Multi-Drug-Resistant Bacteria
Zinc ions have various physiological and biochemical functions, stabilizing the folded conformation of metalloproteins and participating in critical reactions. Zinc can interfere with bacteria in different ways, including zinc overloading and zinc deprivation. In the overloading approach, large volumes of zinc ions are released at the site of bacterial infection using zinc-loaded nanodelivery devices, interfering with bacterial transcriptional control, inactivating functional proteins, producing intracellular ROS and damaging bacterial DNA. Conversely, in the approach of zinc ion deprivation, zinc chelating agents cause an imbalance in zinc ion homeostasis by depriving intracellular zinc ions. Zinc-dependent enzymes become inactive, altering chromatin shape and preventing DNA replication, ultimately leading to bacterial death [79].
Zinc chelation can also potentiate antibiotic activity, as in the case of last-resort carbapenem antibiotics. They belong to the β-lactams class, and nearly all classes can be inactivated by zinc-requiring enzymes called metallo-β-lactamases (MBL) [80]. Bacteria encoding New Delhi MBL (NDM-1) enzymes are among the most fearsome because of the difficulty of treating these infections. Zinc-selective compounds could potentiate β-lactam antibiotics against an MBL-carrying pathogen by withholding zinc availability: Falconer et al. used a mouse model of NDM-1 infection, showing that combination treatment of the respective analog with meropenem resulted in a significant decrease in bacterial burden in contrast to animals that received antibiotic treatment alone [81].
Furthermore, a few bacterial zinc metalloenzymes are gaining interest as targets because they differ from endogenous human zinc-metalloproteinases in every way. The development of novel inhibitors against the enzymes involved in lipid A biosynthesis, bacterial nutrition, and sporulation -such as UDP-[3-O-(R)-3-hydroxymyristoyl]-N-acetylglucosamine deacetylase (LpxC), thermolysin (TLN), and pseudolysin (PLN)—has drawn increasing attention in recent decades from both industry and academia. However, it turns out that targeting these bacterial enzymes is more difficult than anticipated, and the dearth of viable clinical candidates implies that further work is required [82].
3.5. New Experimental Models with Zinc Nanoparticles Against MDR Bacteria
The biosynthesis of metallic nanoparticles has garnered increasing interest due to their favorable attributes, including low toxicity, cost-effectiveness, and ease of large-scale production. Among these, zinc oxide nanoparticles (ZnO-NPs) are particularly promising owing to their intrinsic photocatalytic and photo-oxidative properties, which confer potent antimicrobial activity. They should be considered an emerging and predominantly preclinical research direction rather than an extension of current clinical zinc supplementation strategies. Their relevance lies mainly in the context of antimicrobial resistance and novel anti-infective approaches, and they should be clearly distinguished from oral or systemic zinc supplementation evaluated in included randomized clinical trials.
The reduction in particle size and tailored surface functionalization further enhances their bactericidal efficacy against both Gram-positive and Gram-negative pathogens. Different microbes (bacteria, fungi, and yeast), and various parts of plants (leaf, root, fruit, flower, peel, etc.) have been exploited for the facile, rapid, cost-effective and non-toxic synthesis of ZnONPs [83].
Notably, ZnO-NPs have demonstrated significant potential in the prevention and control of infections caused by multidrug-resistant (MDR) bacteria [84]. The antibacterial efficiency of these particles can be high, yet at low doses (0.16–5.00 mmol/L) [85], with a high bactericidal potential [86].
There are different mechanisms of ZnO-NPs that can be listed: disruption of the cell membrane [87,88], binding to proteins and DNA, generation of reactive oxygen species (ROS) [89,90], disruption of the processes of bacterial DNA amplification, and down-regulation of expression in a wide range of genes [91].
Some authors propose them as an alternative to antibiotics against ESKAPE bacteria, hypothesizing a higher effectiveness and fewer side effects, although these findings should still be validated from a clinical point of view [92].
The literature on ZnO-NPs is rapidly expanding; however, nanoparticles synthesized using different physicochemical methods still face significant limitations that minimize their biocompatibility: the large-scale production of green synthesized ZnO-NPs remains the primary challenge for researchers [93].
3.5.1. Gram-Positive Bacteria
Zinc oxide nanoparticles (ZNO-NPs) proved effective against Gram-positive bacteria such as Staphylococcus aureus, especially methicillin-resistant Staphylococcus aureus (MRSA) strains [94]. Punjabi et al. also assessed the synergistic action of nanoparticles in combination with a common antibiotic, gentamicin (590 g/mg), used to treat various bacterial infections by Checkerboard assay. Zinc oxide nanoparticles synergized with gentamicin only against MRSA but not against other Gram-positive and Gram-negative bacteria [94].
Nejabatdoust et al. evaluated the role of ZnO-NPs in modifying the antibacterial activity of ciprofloxacin (CIP): they found that ZnO-NPs showed a good bacterial inhibitory potential. Moreover, the simultaneous use of modified ZnO-NPs in combination with CIP significantly reduced the expression of the four efflux pumps norA, norB, norC, and tet38 by 5-, 3-, 2-, and 3-fold, respectively, compared to ciprofloxacin alone. Therefore, they suggested that zinc oxide nanoparticles, with their potent antimicrobial effects, could be used as an antimicrobial agent against S. aureus for preventive and/or therapeutic approaches [95].
Djearamane et al. examined the surface interaction between zinc nanoparticles and bacterial cell walls and the subsequent morphological alterations on the bacterial surface in two opportunistic pathogens, Enterococcus faecalis and Serratia marcescens. The growth-inhibitory test showed that ZnO-NPs had a dose-dependent growth-inhibitory impact on both test bacteria; the higher the nanoparticle concentration, the greater the suppression of bacterial growth, especially against E. faecalis [96].
3.5.2. Gram-Negative Bacteria
Whereas some authors reported better results of ZnO-NPs against Gram-positive bacteria [97], others described a higher antibacterial effect against Gram-negative bacteria: probably the effect depends on the characteristics of nanoparticles and their biological synthesis [85]. For example, Elabbasy et al. recently synthesized zinc oxide nanoparticles with a potent, dose-dependent antibacterial and antibiofilm activity against selected MDR E. coli strains isolated from retail fish [98].
Similarly, Chauhan et al. demonstrated that ZnO-NPs could inhibit Pseudomonas aeruginosa [99].
Conversely, combining zinc nanoparticles and antibiotics can synergistically increase the antibacterial efficacy against Gram-negative bacteria, such as in the case of Colistin-resistant Klebsiella pneumoniae, where the synergistic activity of colistin combined with zinc oxide NPs and amikacin against colistin-resistant K. pneumoniae was found to be effective [100].
In the same way, Ghasemi and Jalal found that ZnO-NPs combined with ciprofloxacin and ceftazidime effectively treated Acinetobacter baumannii. A minimum inhibitory concentration (MIC) of 0.25 mg/mL ZnO-NPs boosted the antibacterial activity of both antibiotics by disrupting cell membranes and aggregating antibiotics inside the cells [101].
A key mechanism of zinc nanoparticles involves the disruption of bacterial cell membranes, with their penetration into the bacterial membrane leading to structural damage and eventual cell death [102]. Conversely, the different membrane composition of human cells lessens the possibility that zinc nanoparticles would damage them.
3.5.3. Mycobacteria
Zinc nanoparticles could pierce the complex cell wall of mycobacteria, which is made up of various lipids and mycolic acids, resulting in membrane rupture and cell death.
According to first impressions by Heidary et al., silver and zinc oxide nanoparticles showed bacteriostatic effects against drug-resistant strains of Mycobacterium tuberculosis and thus may be considered promising anti-mycobacterial nano-drugs [103]. Zinc nanoparticles were found effective against Mycobacterium tuberculosis and its MDR strain, with an MIC of 1.25 mg/mL [94].
Geng et al. demonstrated that zinc oxide nanoparticles have biphasic roles on Mycobacterium-induced inflammation by increasing the levels of pro-inflammatory factors (activation of autophagy) and ferroptosis mechanisms in infected macrophages. Using ZnO-NPs improved the anti-Mycobacterium activity of ZnO-NPs in an in vivo mouse model and alleviated acute lung injury caused by ZnO-NPs [104]. These particles can have a synergistic interaction with antibiotics, such as in the case of rifampicin [105], and may act as potential antibacterial agents in future animal and clinical studies.
3.5.4. Biofilm Formation
Bacteria or yeasts that are either Gram-positive or Gram-negative can form biofilms on indwelling catheters. It comprises microbial cells that are discharged into the extracellular space and encased in a self-secreting polymer matrix [106]. The matrix comprises water, proteins, lipids, polysaccharides, and extracellular DNA. In addition to acting as a barrier against the host’s immune defenses, this matrix can prevent antimicrobial medications from penetrating and offers protection from the external environment. Bacteria are gradually liberated from this biofilm, which prolongs the infection and encourages the spread of bacteria to other parts of the body. Because antimicrobial medications have difficulty penetrating the matrix, destroying the biofilm from the central venous catheter (CVC) is particularly difficult. Consequently, CVC removal is the gold standard approach in cases of catheter-related bloodstream infections that do not respond to systemic treatment [107,108,109].
ZnO-NPs can produce reactive oxygen species (ROS) when they encounter microbial cells, which can compromise the integrity of the biofilm matrix. According to Hajipour et al. (2012), these ROS, which include superoxide and hydroxyl radicals, induce oxidative damage to proteins, nucleic acids, extracellular polymeric substances (EPS), and other components of biofilms [110]. This destabilizes the biofilm and eventually results in microbial mortality.
Additionally, ZnO-NPs also have natural anti-adhesive qualities that prevent microorganisms from adhering to surfaces and, hence, stop the formation of biofilms. The electrostatic interactions between ZnO-NPs and microbial cell membranes are responsible for this anti-adhesive effect, which prevents early adhesion to host tissues or medical device surfaces [102].
In particular, Abdelghafar et al. noted that ZnO-NPs had an S. aureus antibiofilm effectiveness, with a synergistic antibiofilm effect of ZnO-NPs in combination with tested antibiotics (gentamycin, clindamycin, cefotaxime, ciprofloxacin, chloramphenicol, and azithromycin). ZnO-NPs were able to lower the hydrophobicity of the S. aureus cell surface, which may account for the observed decline in the capacity of the bacteria to form biofilms. When ZnO-NPs were applied to bacteria, the expression of genes linked to biofilm was much lower than in untreated cells [111].
3.6. Strengths and Limitations
This review summarizes randomized controlled trials (RCTs) on zinc supplementation across all age groups (from neonates to adults) focusing specifically on bacterial infections. A clear distinction was made between therapeutic and prophylactic zinc supplementation, offering a structured understanding of their respective clinical roles. The inclusion of 51 RCTs ensures a comprehensive overview, with robust evidence from diverse geographic and clinical settings.
Emerging therapeutic avenues, such as zinc nanoparticles and their role in combating antimicrobial resistance, were discussed to highlight future research directions.
Among limitations, the heterogeneity of study designs, zinc formulations, dosages, and outcome measures limited the possibility of performing a quantitative meta-analysis. Some included studies had small sample sizes or lacked detailed reporting on secondary outcomes such as laboratory or immune parameters. A key limitation of this scoping review is the absence of a formal risk-of-bias assessment of the included randomized trials, as the primary aim of this scoping review was to map and summarize available evidence rather than formally assess study quality. Furthermore, the evolving field of zinc nanoparticle research is still in preclinical or early clinical stages, with limited high-quality human data available to support firm conclusions.
4. Materials and Methods
4.1. Methodology
This scoping review was conducted according to the PRISMA-ScR (Preferred Reporting Items for Systematic reviews and Meta-Analyses extension for Scoping Reviews) guidelines. A completed PRISMA-ScR checklist is provided in Supplementary File S1. No review protocol was registered for this scoping review.
4.2. Eligibility Criteria
We included RCTs written in English and reporting clinical outcomes related to bacterial infections following zinc supplementation in neonates, children, or adults. We excluded observational studies, studies without infection-related outcomes, non-human studies, and trials where zinc was not administered as a distinct intervention. The time window (2000–1 November 2025) was chosen to capture contemporary dosing strategies and outcome definitions. Randomized controlled trials were specifically selected to minimize confounding and better assess causal relationships between zinc supplementation and infection-related outcomes. While this approach may limit the breadth of available evidence, we believe that it can increase internal validity and strengthen the interpretability of clinical effects.
4.3. Information Sources
We searched MEDLINE (PubMed) for eligible studies. The search covered the period from 2000, to 1 November 2025. Reference lists of included articles were also screened to identify additional relevant studies.
4.4. Search Strategy and Selection of Sources of Evidence
The PubMed search was conducted using the following terms: “zinc” AND (“neonate” OR “infant” OR “child” OR “adult”) AND (“bacterial infection” OR “sepsis” OR “pneumonia” OR “diarrhea”). Only English manuscripts and RCTs were considered. Two authors (D.U.D.R. and L.C.) independently assessed the study eligibility according to the pre-established criteria and performed an accurate check to exclude duplicates. Discussion with a third researcher (M.I.) resolved differences in opinion to achieve consensus.
4.5. Data Charting Process and Data Items
Data from each included RCT were charted using a standardized extraction form developed for this review. The form captured study design, population, intervention characteristics, dosing regimen, outcomes related to bacterial infections, and key findings. Data charting was conducted independently by two reviewers (D.U.D.R. and L.C.), and discrepancies were resolved through discussion with a third researcher (M.I.). For each study, we extracted the following variables: country and year, population characteristics (age group, clinical condition), type of supplementation (therapeutic or prophylactic), and main outcomes (e.g., sepsis, pneumonia, diarrhea, inflammatory markers, mortality).
4.6. Critical Appraisal of Individual Sources
Given the heterogeneity of study designs, populations, zinc formulations, and outcome measures, no quantitative synthesis or meta-analysis was performed, in line with the aims of a scoping review.
4.7. Outcomes
The objective was to map the breadth and nature of the available evidence on zinc supplementation and its role in bacterial infections across different age groups. Concerning the evidence from RCTs, our primary outcome was the effect of zinc supplementation on infections, whereas our secondary outcomes included laboratory changes. We focused specifically on bacterial infectious outcomes and distinguished between therapeutic and prophylactic zinc supplementation across age groups. Furthermore, we explored emerging research directions involving antimicrobial resistance and zinc-based nanotechnologies.
5. Conclusions
Zinc supplementation, both therapeutic and prophylactic, has demonstrated significant benefits in reducing the incidence, severity, and duration of infections, especially in neonates, children, and immunocompromised adults. With zinc deficiency still prevalent globally, especially in high-risk populations, its correction is essential for optimal immune function.
Beyond its immunomodulatory effects, zinc may play a key role in addressing antimicrobial resistance. Zinc oxide nanoparticles (ZnO-NPs) show promises as adjunct therapies due to their ability to disrupt bacterial growth, enhance antibiotic activity, and prevent biofilm formation.
Further research is needed to establish standardized dosing strategies to prevent and restore zinc deficiency and evaluate the short-term and long-term safety and efficacy of novel zinc-based interventions, including nanoparticles, in clinical settings.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/antibiotics15010066/s1, File S1: PRISMA-ScR-Fillable-Checklist. Ref. [112] is cited in the Supplementary Materials.
Author Contributions
Conceptualization, D.U.D.R. and M.I.; methodology, D.U.D.R.; software, D.U.D.R.; formal analysis, D.U.D.R., L.C., and M.I.; investigation, D.U.D.R., N.M., L.C., and M.I.; data curation, D.U.D.R., N.M., L.C., and M.I.; writing—original draft preparation, D.U.D.R.; writing—review and editing, N.M., A.D., G.S., M.P.R., L.C., F.C.-S., and M.I.; supervision, A.D. and M.I. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by the Italian Ministry of Health with “Current Research” funds.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ALRI | Acute lower respiratory infection |
| CA | Corrected age |
| CF | Cystic fibrosis |
| CIP | Ciprofloxacin |
| CI | Confidence interval |
| CRP | C-reactive protein |
| CVC | Central venous catheter |
| EOS | Early-onset sepsis |
| EPS | Extracellular polymeric substances |
| GA | Gestational age |
| HIV | Human immunodeficiency virus |
| IL-6 | Interleukin-6 |
| KIR | Killer-cell Ig-like receptor |
| LBW | Low birth weight |
| LOS | Late-onset sepsis |
| LpxC | UDP-[3-O-(R)-3-hydroxymyristoyl]-N-acetylglucosamine deacetylase |
| MBL | Metallo-β-lactamase |
| MDR | Multidrug-resistant |
| MHC-I | Major histocompatibility complex class I |
| MIC | Minimum inhibitory concentration |
| MRSA | Methicillin-resistant Staphylococcus aureus |
| NCT | ClinicalTrials.gov identifier |
| NDM-1 | New Delhi metallo-β-lactamase 1 |
| NEC | Necrotizing enterocolitis |
| NK cells | Natural killer cells |
| PICU | Pediatric intensive care unit |
| PCT | Procalcitonin |
| PLN | Pseudolysin |
| PRISMA-ScR | Preferred Reporting Items for Systematic reviews and Meta-Analyses extension for Scoping Reviews |
| RCT/RCTs | Randomized controlled trial/Randomized controlled trials |
| ROS | Reactive oxygen species |
| RR | Relative risk |
| SBI | Serious bacterial illness |
| SCA | Sickle cell anemia |
| SEM | Scanning electron microscopy |
| TB | Tuberculosis |
| Th1/Th2 | T helper 1/T helper 2 |
| TLN | Thermolysin |
| URTI | Upper respiratory tract infection |
| Zn | Zinc |
| Zn2+ | Zinc ion |
| ZnO-NPs | Zinc oxide nanoparticles |
| ZnuA/ZnuB/ZnuC | Components of the ZnuABC zinc import system |
| ZIP14 | Zinc transporter protein 14 |
References
- Prasad, A.S. Discovery of Human Zinc Deficiency: Its Impact on Human Health and Disease. Adv. Nutr. 2013, 4, 176–190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wessells, K.R.; Brown, K.H. Estimating the Global Prevalence of Zinc Deficiency: Results Based on Zinc Availability in National Food Supplies and the Prevalence of Stunting. PLoS ONE 2012, 7, e50568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stiles, L.I.; Ferrao, K.; Mehta, K.J. Role of Zinc in Health and Disease. Clin. Exp. Med. 2024, 24, 38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rizwan, M.; Cheng, K.; Gang, Y.; Hou, Y.; Wang, C. Immunomodulatory Effects of Vitamin D and Zinc on Viral Infection. Biol. Trace Elem. Res. 2025, 203, 1–17. [Google Scholar] [CrossRef] [Scilit]
- Matar, A.; Damianos, J.A.; Jencks, K.J.; Camilleri, M. Intestinal Barrier Impairment, Preservation, and Repair: An Update. Nutrients 2024, 16, 3494. [Google Scholar] [CrossRef] [Scilit]
- Kim, B.; Lee, W.W. Regulatory Role of Zinc in Immune Cell Signaling. Mol. Cells 2021, 44, 335–341. [Google Scholar] [CrossRef] [Scilit]
- Maares, M.; Haase, H. Zinc and Immunity: An Essential Interrelation. Arch. Biochem. Biophys. 2016, 611, 58–65. [Google Scholar] [CrossRef] [Scilit]
- Marreiro, D.d.N.; Cruz, K.J.C.; Morais, J.B.S.; Beserra, J.B.; Severo, J.S.; Soares de Oliveira, A.R. Zinc and Oxidative Stress: Current Mechanisms. Antioxidants 2017, 6, 24. [Google Scholar] [CrossRef] [Scilit]
- Passarelli, S.; Free, C.M.; Shepon, A.; Beal, T.; Batis, C.; Golden, C.D. Global Estimation of Dietary Micronutrient Inadequacies: A Modelling Analysis. Lancet Glob. Health 2024, 12, e1590–e1599. [Google Scholar] [CrossRef] [Scilit]
- Beker Aydemir, T.; Chang, S.M.; Guthrie, G.J.; Maki, A.B.; Ryu, M.S.; Karabiyik, A.; Cousins, R.J. Zinc Transporter ZIP14 Functions in Hepatic Zinc, Iron and Glucose Homeostasis during the Innate Immune Response (Endotoxemia). PLoS ONE 2012, 7, e48679. [Google Scholar] [CrossRef] [Scilit]
- Maywald, M.; Rink, L. Zinc in Human Health and Infectious Diseases. Biomolecules 2022, 12, 1748. [Google Scholar] [CrossRef] [Scilit]
- Bhatnagar, S.; Wadhwa, N.; Aneja, S.; Lodha, R.; Kabra, S.K.; Natchu, U.C.M.; Sommerfelt, H.; Dutta, A.K.; Chandra, J.; Rath, B.; et al. Zinc as Adjunct Treatment in Infants Aged between 7 and 120 Days with Probable Serious Bacterial Infection: A Randomised, Double-Blind, Placebo-Controlled Trial. Lancet 2012, 379, 2072–2078. [Google Scholar] [CrossRef] [Scilit]
- Mehta, K.; Bhatta, N.K.; Majhi, S.; Shrivastava, M.K.; Singh, R.R. Oral Zinc Supplementation for Reducing Mortality in Probable Neonatal Sepsis: A Double Blind Randomized Placebo Controlled Trial. Indian Pediatr 2013, 50, 390–393. [Google Scholar] [CrossRef] [Scilit]
- Banupriya, N.; Bhat, B.V.; Dhas, B.B.; Mondal, N.; Gopalakrishna, S.M. Effect of Zinc Supplementation on Early Outcome of Neonatal Sepsis—A Randomized Controlled Trial. Indian J. Pediatr. 2016, 83, 289–293. [Google Scholar] [CrossRef] [Scilit]
- El Farargy, M.S.; Soliman, N.A. Zinc Supplementation as an Adjuvant Treatment in Neonatal Sepsis. Curr. Pediatr. Res. 2017, 21, 93–98. [Google Scholar]
- Elfarargy, M.S.; Al-Ashmawy, G.; Abu-Risha, S.; Khattab, H. Zinc Supplementation in Preterm Neonates with Late-Onset Sepsis: Is It Beneficial? Am. J. Perinatol. 2020, 39, 1097–1103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wadhwa, N.; Sinha, A.; Basnet, S.; Arya, S.; Singh, R.; Jajoo, M.; Ayushi; Sharma, D.; Kumar, A.; Pemde, H.K.; et al. Zinc as Adjunct Treatment for Clinical Severe Infection in Young Infants: A Randomized Double-Blind Placebo-Controlled Trial in India and Nepal. PLoS Med. 2025, 22, e1004759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Terrin, G.; Canani, R.B.; Passariello, A.; Messina, F.; Conti, M.G.; Caoci, S.; Smaldore, A.; Bertino, E.; De Curtis, M. Zinc Supplementation Reduces Morbidity and Mortality in Very-Lowbirth-Weight Preterm Neonates: A Hospital-Based Randomized, Placebo-Controlled Trial in an Industrialized Country. Am. J. Clin. Nutr. 2013, 98, 1468–1474. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mathur, N.; Agarwal, D.K. Zinc Supplementation in Preterm Neonates and Neurological Development: A Randomized Controlled Trial. Indian Pediatr. 2015, 52, 951–955. [Google Scholar] [CrossRef] [Scilit]
- Habib, M.A.; Soofi, S.; Sheraz, A.; Bhatti, Z.S.; Okayasu, H.; Zaidi, S.Z.; Molodecky, N.A.; Pallansch, M.A.; Sutter, R.W.; Bhutta, Z.A. Zinc Supplementation Fails to Increase the Immunogenicity of Oral Poliovirus Vaccine: A Randomized Controlled Trial. Vaccine 2015, 33, 819–825. [Google Scholar] [CrossRef] [Scilit]
- Sahin, S.; Sari, F.N.; Bidev, D.; Bozkurt, O.; Dizdar, E.A.; Oguz, S.S. Zinc Supplementation in Very Low Birth Weight Infants: A Randomized Controlled Trial. Am. J. Perinatol. 2024, 41, E3107–E3114. [Google Scholar] [CrossRef] [Scilit]
- Irfan, O.; Black, E.; Lassi, Z.S.; Bhutta, A. Zinc Supplementation and the Prevention and Treatment of Sepsis in Young Infants: A Systematic Review and Meta-Analysis. Neonatology 2022, 119, 164–175. [Google Scholar] [CrossRef] [Scilit]
- Sazawal, S.; Black, R.E.; Bhan, M.K.; Bhandari, N.; Sinha, A.; Jalla, S. Zinc Supplementation in Young Children with Acute Diarrhea in India. N. Engl. J. Med. 1995, 333, 839–844. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhutta, Z.A.; Nizami, S.Q.; Isani, Z. Zinc Supplementation in Malnourihed Children with Persistent Diarrhea in Pakistan. Pediatrics 1999, 103, e42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Penny, M.E.; Peerson, J.M.; Marin, R.M.; Duran, A.; Lanata, C.F.; Lonnerdal, B.; Black, R.E.; Brown, K.H. Randomized, Community-Based Trial of the Effect of Zinc Supplementation, with and without Other Micronutrients, on the Duration of Persistent Childhood Diarrhea in Lima, Peru. J. Pediatr. 1999, 135, 208–217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baqui, A.H.; Black, R.E.; El Arifeen, S.; Yunus, M.; Chakraborty, J.; Ahmed, S.; Vaughan, J.P. Effect of Zinc Supplementation Started during Diarrhoea on Morbidity and Mortality in Bangladeshi Children: Community Randomised Trial. Br. Med. J. 2002, 325, 1059–1062. [Google Scholar] [CrossRef] [Scilit]
- Brooks, W.A.; Yunus, M.; Santosham, M.; Wahed, M.A.; Nahar, K.; Yeasmin, S.; Black, R.E. Zinc for Severe Pneumonia in Very Young Children: Double-Blind Placebo-Controlled Trial. Lancet 2004, 363, 1683–1688. [Google Scholar] [CrossRef] [Scilit]
- Raqib, R.; Roy, S.K.; Rahman, M.J.; Azim, T.; Ameer, S.S.; Chisti, J.; Andersson, J. Effect of Zinc Supplementation on Immune and Inflammatory Responses in Pediatric Patients with Shigellosis. Am. J. Clin. Nutr. 2004, 79, 444–450. [Google Scholar] [CrossRef] [Scilit]
- Mahalanabis, D.; Lahiri, M.; Paul, D.; Gupta, S.; Gupta, A.; Wahed, M.A.; Khaled, M.A. Randomized, Double-Blind, Placebo-Controlled Clinical Trial of the Efficacy of Treatment with Zinc or Vitamin A in Infants and Young Children with Severe Acute Lower Respiratory Infection. Am. J. Clin. Nutr. 2004, 79, 430–436. [Google Scholar] [CrossRef] [Scilit]
- Patel, A.B.; Dhande, L.A.; Rawat, M.S. Therapeutic Evaluation of Zinc and Copper Supplementation in Acute Diarrhea in Children: Double Blind Randomized Trial. Indian Pediatr 2005, 42, 433–442. [Google Scholar]
- Roy, S.K.; Tomkins, A.M.; Akramuzzaman, S.M.; Chakraborty, B.; Ara, G.; Biswas, R.; Islam, K.E.; Khatun, W.; Jolly, S.P. Impact of Zinc Supplementation on Subsequent Morbidity and Growth in Bangladeshi Children with Persistent Diarrhoea. J. Health Popul. Nutr. 2007, 25, 67–74. [Google Scholar] [PubMed]
- Patel, A.; Dibley, M.J.; Mamtani, M.; Badhoniya, N.; Kulkarni, H. Zinc and Copper Supplementation in Acute Diarrhea in Children: A Double-Blind Randomized Controlled Trial. BMC Med. 2009, 7, 22. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dutta, P.; Mitra, U.; Dutta, S.; Naik, T.N.; Rajendran, K.; Chatterjee, M.K. Zinc, Vitamin A, and Micronutrient Supplementation in Children with Diarrhea: A Randomized Controlled Clinical Trial of Combination Therapy versus Monotherapy. J. Pediatr. 2011, 159, 633–637. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, G.S.; Dutta, A.K.; Shah, D.; Mishra, O.P. Role of Zinc in Severe Pneumonia: A Randomized Double Bind Placebo Controlled Study. Ital. J. Pediatr. 2012, 38, 36. [Google Scholar] [CrossRef] [Scilit]
- Shah, U.H.; Abu-Shaheen, A.K.; Malik, M.A.; Alam, S.; Riaz, M.; AL-Tannir, M.A. The Efficacy of Zinc Supplementation in Young Children with Acute Lower Respiratory Infections: A Randomized Double-Blind Controlled Trial. Clin. Nutr. 2013, 32, 193–199. [Google Scholar] [CrossRef] [Scilit]
- Yazar, A.S.; Guven, Ş.; Dinleyici, E.Ç. Effects of Zinc or Synbiotic on the Duration of Diarrhea in Children with Acute Infectious Diarrhea. Turk. J. Gastroenterol. 2016, 27, 537–540. [Google Scholar] [CrossRef] [Scilit]
- Yousefichaijan, P.; Naziri, M.; Taherahmadi, H.; Kahbazi, M.; Tabaei, A. Zinc Supplementation in Treatment of Children with Urinary Tract Infection. Iran J. Kidney Dis. 2016, 10, 213–216. [Google Scholar]
- Howie, S.; Bottomley, C.; Chimah, O.; Ideh, R.; Ebruke, B.; Okomo, U.; Onyeama, C.; Donkor, S.; Rodrigues, O.; Tapgun, M.; et al. Zinc as an Adjunct Therapy in the Management of Severe Pneumonia among Gambian Children: Randomized Controlled Trial. J. Glob. Health 2018, 8, 010418. [Google Scholar] [CrossRef] [Scilit]
- Rerksuppaphol, L.; Rerksuppaphol, S. Efficacy of Adjunctive Zinc in Improving the Treatment Outcomes in Hospitalized Children with Pneumonia: A Randomized Controlled Trial. J. Trop. Pediatr. 2020, 66, 419–427. [Google Scholar] [CrossRef] [Scilit]
- Dhingra, U.; Kisenge, R.; Sudfeld, C.R.; Dhingra, P.; Somji, S.; Dutta, A.; Bakari, M.; Deb, S.; Devi, P.; Liu, E.; et al. Lower-Dose Zinc for Childhood Diarrhea—A Randomized, Multicenter Trial. N. Engl. J. Med. 2020, 383, 1231–1241. [Google Scholar] [CrossRef] [Scilit]
- Rosado, J.L.; Lopez, P.; Munoz, E.; Martinez, H.; Allen, L.H. Zinc Supplementation Reduced Morbidity, but Neither Zinc nor Iron Supplementation Affected Growth or Body Composition of Mexican Preschoolers. Am. J. Clin. Nutr. 1997, 65, 13–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruel, M.T.; Rivera, J.A.; Santizo, M.; Lo, B.; Brown, K.H. Impact of Zinc Supplementation on Morbidity From Diarrhea and Respiratory Infections Among Rural Guatemalan Children. Pediatrics 1997, 99, 808–813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sazawal, S.; Black, R.E.; Jalla, S.; Mazumdar, S.; Sinha, A.; Bhan, M.K. Zinc Supplementation Reduces the Incidence of Acute Lower Respiratory Infections in Infants and Preschool Children: A Double-Blind, Controlled Trial. Pediatrics 1998, 102, 1–5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bobat, R.; Coovadia, H.; Stephen, C.; Naidoo, K.L.; McKerrow, N.; Black, R.E.; Moss, W.J. Safety and Efficacy of Zinc Supplementation for Children with HIV-1 Infection in South Africa: A Randomised Double-Blind Placebo-Controlled Trial. Lancet 2005, 366, 1862–1867. [Google Scholar] [CrossRef] [Scilit]
- Long, K.Z.; Montoya, Y.; Hertzmark, E.; Santos, J.I.; Rosado, J.L. A Double-Blind, Randomized, Clinical Trial of the Effect of Vitamin A and Zinc Supplementation on Diarrheal Disease and Respiratory Tract Infections in Children in Mexico City, Mexico. Am. J. Clin. Nutr. 2006, 83, 693–700. [Google Scholar] [CrossRef] [Scilit]
- Abdulhamid, I.; Beck, F.W.J.; Miliard, S.; Chen, X.; Prasad, A. Effect of Zinc Supplementation on Respiratory Tract Infections in Children with Cystic Fibrosis. Pediatr. Pulmonol. 2008, 43, 281–287. [Google Scholar] [CrossRef] [Scilit]
- Consolo, L.Z.Z.; Melnikov, P.; Cônsolo, F.Z.; Nascimento, V.A.; Pontes, J.C.D.V. Zinc Supplementation in Children and Adolescents with Acute Leukemia. Eur. J. Clin. Nutr. 2013, 67, 1056–1059. [Google Scholar] [CrossRef] [Scilit]
- Malik, A.; Taneja, D.K.; Devasenapathy, N.; Rajeshwari, K. Short-Course Prophylactic Zinc Supplementation for Diarrhea Morbidity in Infants of 6 to 11 Months. Pediatrics 2013, 132, e46–e52. [Google Scholar] [CrossRef] [Scilit]
- Lodha, R.; Shah, N.; Mohari, N.; Mukherjee, A.; Vajpayee, M.; Singh, R.; Singla, M.; Saini, S.; Bhatnagar, S.; Kabra, S.K. Immunologic Effect of Zinc Supplementation in HIV-Infected Children Receiving Highly Active Antiretroviral Therapy: A Randomized, Double-Blind, Placebo-Controlled Trial. J. Acquir. Immune Defic. Syndr. 2014, 66, 386–392. [Google Scholar] [CrossRef] [Scilit]
- McDonald, C.M.; Manji, K.P.; Kisenge, R.; Aboud, S.; Spiegelman, D.; Fawzi, W.W.; Duggan, C.P. Daily Zinc but Not Multivitamin Supplementation Reduces Diarrhea and Upper Respiratory Infections in Tanzanian Infants: A Randomized, Double-Blind, Placebo-Controlled Clinical Trial. J. Nutr. 2015, 145, 2153–2160. [Google Scholar] [CrossRef] [Scilit]
- Martinez-Estevez, N.S.; Alvarez-Guevara, A.N.; Rodriguez-Martinez, C.E. Effects of Zinc Supplementation in the Prevention of Respiratory Tract Infections and Diarrheal Disease in Colombian Children: A 12-Month Randomised Controlled Trial. Allergol. Immunopathol. 2016, 44, 368–375. [Google Scholar] [CrossRef] [Scilit]
- Sharma, G.; Lodha, R.; Shastri, S.; Saini, S.; Kapil, A.; Singla, M.; Mukherjee, A.; Jat, K.R.; Kabra, M.; Kabra, S.K. Zinc Supplementation for One Year among Children with Cystic Fibrosis Does Not Decrease Pulmonary Infection. Respir. Care 2016, 61, 78–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carcillo, J.A.; Dean, J.M.; Holubkov, R.; Berger, J.; Meert, K.L.; Anand, K.J.S.; Zimmerman, J.J.; Newth, C.J.L.; Harrison, R.; Burr, J.; et al. Interaction Between 2 Nutraceutical Treatments and Host Immune Status in the Pediatric Critical Illness Stress-Induced Immune Suppression Comparative Effectiveness Trial. J. Parenter. Enter. Nutr. 2017, 41, 1325–1335. [Google Scholar] [CrossRef] [Scilit]
- Namazzi, R.; Opoka, R.; Conroy, A.L.; Datta, D.; Tagoola, A.; Bond, C.; Goings, M.J.; Ryu, M.S.; Cusick, S.E.; Krebs, N.F.; et al. Zinc for Infection Prevention in Children with Sickle Cell Anemia: A Randomized Double-Blind Placebo-Controlled Trial. Blood Adv 2023, 7, 3023–3031. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berger, M.M.; Eggimann, P.; Heyland, D.K.; Chioléro, R.L.; Revelly, J.P.; Day, A.; Raffoul, W.; Shenkin, A. Reduction of Nosocomial Pneumonia after Major Burns by Trace Element Supplementation: Aggregation of Two Randomised Trials. Crit. Care 2006, 10, 6–12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baum, M.K.; Lai, S.; Sales, S.; Page, J.B.; Campa, A. Randomized, Controlled Clinical Trial of Zinc Supplementation to Prevent Immunological Failure in HIV-Infected Adults. Clin. Infect. Dis. 2010, 50, 1653–1660. [Google Scholar] [CrossRef] [Scilit]
- Ejemot-Nwadiaro, R.I.; Itam, E.H.; Ezedinachi, E.N. Zinc Supplementation as Adjunctive Therapy in Adults with Tuberculosis in Calabar, Nigeria: A Randomized Controlled Trial. J. Adv. Med. Med. Res. 2019, 29, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Ertekin, M.V.; Uslu, H.; Karslioglu, I.; Ozbek, E.; Ozbek, A. Effect of Oral Zinc Supplementation on Agents of Oropharyngeal Infection in Patients Receiving Radiotherapy for Head and Neck Cancer. J. Int. Med. Res. 2003, 31, 253–266. [Google Scholar] [CrossRef] [Scilit]
- Deloria-Knoll, M.; Steinhoff, M.; Semba, R.D.; Nelson, K.; Vlahov, D.; Meinert, C.L. Effect of Zinc and Vitamin A Supplementation on Antibody Responses to a Pneumococcal Conjugate Vaccine in HIV-Positive Injection Drug Users: A Randomized Trial. Vaccine 2006, 24, 1670–1679. [Google Scholar] [CrossRef] [Scilit]
- Prasad, A.S.; Beck, F.W.J.; Bao, B.; Fitzgerald, J.T.; Snell, D.C.; Steinberg, J.D.; Cardozo, L.J. Zinc Supplementation Decreases Incidence of Infections in the Elderly: Effect of Zinc on Generation of Cytokines and Oxidative Stress. Am. J. Clin. Nutr. 2007, 85, 837–844. [Google Scholar] [CrossRef] [Scilit]
- Asdamongkol, N.; Phanachet, P.; Sungkanuparph, S. Low Plasma Zinc Levels and Immunological Responses to Zinc Supplementation in HIV-Infected Patients with Immunological Discordance after Antiretroviral Therapy. Jpn. J. Infect. Dis. 2013, 66, 469–474. [Google Scholar] [CrossRef] [Scilit]
- Hadadi, A.; Ostovar, A.; Edalat Noor, B.; Rasoolinejad, M.; Haji Abdolbaghi, M.; Yousefi, S.; Khalili, H.; Manshoori, G.; Khashayar, P.; Alipour, Z.; et al. The Effect of Selenium and Zinc on CD4(+) Count and Opportunistic Infections in HIV/AIDS Patients: A Randomized Double Blind Trial. Acta Clin. Belg. Int. J. Clin. Lab. Med. 2020, 75, 170–176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silva, M.; Montes, C.G.; Canals, A.; MacKenna, M.J.; Wolff, M. Role and Effects of Zinc Supplementation in HIV-Infected Patients with Immunovirological Discordance: A Randomized, Double Blind, Case Control Study. PLoS ONE 2021, 16, e0244823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stevens, G.A.; Beal, T.; Mbuya, M.N.N.; Luo, H.; Neufeld, L.M.; Addo, O.Y.; Adu-Afarwuah, S.; Alayón, S.; Bhutta, Z.; Brown, K.H.; et al. Micronutrient Deficiencies among Preschool-Aged Children and Women of Reproductive Age Worldwide: A Pooled Analysis of Individual-Level Data from Population-Representative Surveys. Lancet Glob. Health 2022, 10, e1590–e1599. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Littlejohn, P.T.; Metcalfe-Roach, A.; Cardenas Poire, E.; Holani, R.; Bar-Yoseph, H.; Fan, Y.M.; Woodward, S.E.; Finlay, B.B. Multiple Micronutrient Deficiencies in Early Life Cause Multi-Kingdom Alterations in the Gut Microbiome and Intrinsic Antibiotic Resistance Genes in Mice. Nat. Microbiol. 2023, 8, 2392–2405. [Google Scholar] [CrossRef] [Scilit]
- Wessels, I.; Maywald, M.; Rink, L. Zinc as a Gatekeeper of Immune Function. Nutrients 2017, 9, 9–12. [Google Scholar] [CrossRef] [Scilit]
- Uciechowski, P.; Kahmann, L.; Plümäkers, B.; Malavolta, M.; Mocchegiani, E.; Dedoussis, G.; Herbein, G.; Jajte, J.; Fulop, T.; Rink, L. TH1 and TH2 Cell Polarization Increases with Aging and Is Modulated by Zinc Supplementation. Exp. Gerontol. 2008, 43, 493–498. [Google Scholar] [CrossRef] [Scilit]
- Haase, H.; Mocchegiani, E.; Rink, L. Correlation between Zinc Status and Immune Function in the Elderly. Biogerontology 2006, 7, 421–428. [Google Scholar] [CrossRef] [Scilit]
- Kahmann, L.; Uciechowski, P.; Warmuth, S.; Plümäkers, B.; Gressner, A.M.; Malavolta, M.; Mocchegiani, E.; Rink, L. Zinc Supplementation in the Elderly Reduces Spontaneous Inflammatory Cytokine Release and Restores T Cell Functions. Rejuvenation Res. 2008, 11, 227–237. [Google Scholar] [CrossRef] [Scilit]
- Hasan, R.; Rink, L.; Haase, H. Chelation of Free Zn2+ Impairs Chemotaxis, Phagocytosis, Oxidative Burst, Degranulation, and Cytokine Production by Neutrophil Granulocytes. Biol. Trace Elem. Res. 2016, 171, 79–88. [Google Scholar] [CrossRef] [Scilit]
- Kumar, S.; Rajagopalan, S.; Sarkar, P.; Dorward, D.W.; Peterson, M.E.; Liao, H.S.; Guillermier, C.; Steinhauser, M.L.; Vogel, S.S.; Long, E.O. Zinc-Induced Polymerization of Killer-Cell Ig-like Receptor into Filaments Promotes Its Inhibitory Function at Cytotoxic Immunological Synapses. Mol. Cell 2016, 62, 21–33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rouhani, P.; Rezaei Kelishadi, M.; Saneei, P. Effect of Zinc Supplementation on Mortality in under 5-Year Children: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Eur. J. Nutr. 2022, 61, 37–54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Banupriya, N.; Bhat, B.V.; Sridhar, M.G. Role of Zinc in Neonatal Sepsis. Indian J. Pediatr. 2021, 88, 696–702. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lassi, Z.S.; Haider, B.A.; Bhutta, Z.A. Zinc Supplementation for the Prevention of Pneumonia in Children Aged 2 Months to 59 Months. Cochrane Database Syst. Rev. 2010, 12, CD005978. [Google Scholar] [CrossRef] [Scilit]
- Lotfi, Z.; Zeraati, A.A.; Dashti, E.; Zeraati, T.; Arghiany, M.; Kalani-Moghaddam, F.; Haghighi, A. Zinc Deficiency May Play a Crucial Role in Dialysis-Associated Bacterial Infections. J. Ren. Inj Prev. 2022, 11, e09. [Google Scholar] [CrossRef] [Scilit]
- Meydani, S.N.; Barnett, J.B.; Dallal, G.E.; Fine, B.C.; Jacques, P.F.; Leka, L.S.; Hamer, D.H. Serum Zinc and Pneumonia in Nursing Home Elderly. Am. J. Clin. Nutr. 2007, 86, 1167–1173. [Google Scholar] [CrossRef] [Scilit]
- Ortega, E.F.; Wu, D.; Guo, W.; Meydani, S.N.; Panda, A. Study Protocol for a Zinc Intervention in the Elderly for Prevention of Pneumonia, a Randomized, Placebo-Controlled, Double-Blind Clinical Pilot Trial. Front. Nutr. 2024, 11, 1356594. [Google Scholar] [CrossRef] [Scilit]
- Kiabi, F.H.; Alipour, A.; Darvishi-Khezri, H.; Aliasgharian, A.; Zeydi, A.E. Zinc Supplementation in Adult Mechanically Ventilated Trauma Patients Is Associated with Decreased Occurrence of Ventilator-Associated Pneumonia: A Secondary Analysis of a Prospective, Observational Study. Indian J. Crit. Care Med. 2017, 21, 34–39. [Google Scholar] [CrossRef] [Scilit]
- Wei, Y.; Wang, J.; Wu, S.; Zhou, R.; Zhang, K.; Zhang, Z.; Liu, J.; Qin, S.; Shi, J. Nanomaterial-Based Zinc Ion Interference Therapy to Combat Bacterial Infections. Front. Immunol. 2022, 13, 899992. [Google Scholar] [CrossRef] [Scilit]
- Palzkill, T. Metallo-β-Lactamase Structure and Function. Ann. N. Y. Acad. Sci. 2013, 1277, 91–104. [Google Scholar] [CrossRef] [Scilit]
- Falconer, S.B.; Reid-Yu, S.A.; King, A.M.; Gehrke, S.S.; Wang, W.; Britten, J.F.; Coombes, B.K.; Wright, G.D.; Brown, E.D. Zinc Chelation by a Small-Molecule Adjuvant Potentiates Meropenem Activity in Vivo against NDM-1-Producing Klebsiella Pneumoniae. ACS Infect. Dis. 2016, 1, 533–543. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Leo, R.; Cuffaro, D.; Rossello, A.; Nuti, E. Bacterial Zinc Metalloenzyme Inhibitors: Recent Advances and Future Perspectives. Molecules 2023, 28, 4378. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huq, M.A.; Apu, M.A.I.; Ashrafudoulla, M.; Rahman, M.M.; Parvez, M.A.K.; Balusamy, S.R.; Akter, S.; Rahman, M.S. Bioactive ZnO Nanoparticles: Biosynthesis, Characterization and Potential Antimicrobial Applications. Pharmaceutics 2023, 15, 2634. [Google Scholar] [CrossRef] [Scilit]
- Gharpure, S.; Ankamwar, B. Synthesis and Antimicrobial Properties of Zinc Oxide Nanoparticles. J. Nanosci. Nanotechnol. 2020, 20, 5977–5996. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gudkov, S.V.; Burmistrov, D.E.; Serov, D.A.; Rebezov, M.B.; Semenova, A.A.; Lisitsyn, A.B. A Mini Review of Antibacterial Properties of ZnO Nanoparticles. Front. Phys. 2021, 9, 641481. [Google Scholar] [CrossRef] [Scilit]
- Azam, A.; Ahmed, A.S.; Oves, M.; Khan, M.S.; Habib, S.S.; Memic, A. Antimicrobial Activity of Metal Oxide Nanoparticles against Gram-Positive and Gram-Negative Bacteria: A Comparative Study. Int. J. Nanomed. 2012, 7, 6003–6009. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.; He, L.; Mustapha, A.; Li, H.; Hu, Z.Q.; Lin, M. Antibacterial Activities of Zinc Oxide Nanoparticles against Escherichia Coli O157:H7. J. Appl. Microbiol. 2009, 107, 1193–1201. [Google Scholar] [CrossRef] [Scilit]
- Sirelkhatim, A.; Mahmud, S.; Seeni, A.; Kaus, N.H.M.; Ann, L.C.; Bakhori, S.K.M.; Hasan, H.; Mohamad, D. Review on Zinc Oxide Nanoparticles: Antibacterial Activity and Toxicity Mechanism. Nanomicro Lett. 2015, 7, 219–242. [Google Scholar] [CrossRef] [Scilit]
- Saha, R.K.; Debanath, M.K.; Paul, B.; Medhi, S.; Saikia, E. Antibacterial and Nonlinear Dynamical Analysis of Flower and Hexagon-Shaped ZnO Microstructures. Sci. Rep. 2020, 10, 2598. [Google Scholar] [CrossRef] [Scilit]
- Dutta, R.K.; Nenavathu, B.P.; Gangishetty, M.K.; Reddy, A.V.R. Studies on Antibacterial Activity of ZnO Nanoparticles by ROS Induced Lipid Peroxidation. Colloids Surf. B Biointerfaces 2012, 94, 143–150. [Google Scholar] [CrossRef] [Scilit]
- Xie, Y.; He, Y.; Irwin, P.L.; Jin, T.; Shi, X. Antibacterial Activity and Mechanism of Action of Zinc Oxide Nanoparticles against Campylobacter Jejuni. Appl. Environ. Microbiol. 2011, 77, 2325–2331. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soleymanzadeh Moghadam, S.; Doust, R.H.; Majidpour, A.; Adabi, M.; Minaeian, S. Antibacterial Activity and Toxicity of Zinc Oxide Nanoparticles Combined with Supernatants of Lactobacillus Spp. Against ESKAPE Bacteria: A Novel Mixture. Iran. J. Pharm. Res. 2023, 22, e139222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mishra, A.; Pradhan, D.; Halder, J.; Biswasroy, P.; Rai, V.K.; Dubey, D.; Kar, B.; Ghosh, G.; Rath, G. Metal Nanoparticles against Multi-Drug-Resistance Bacteria. J. Inorg. Biochem. 2022, 237, 111938. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Punjabi, K.; Mehta, S.; Chavan, R.; Chitalia, V.; Deogharkar, D.; Deshpande, S. Efficiency of Biosynthesized Silver and Zinc Nanoparticles against Multi-Drug Resistant Pathogens. Front. Microbiol. 2018, 9, 2207. [Google Scholar] [CrossRef] [Scilit]
- Nejabatdoust, A.; Zamani, H.; Salehzadeh, A. Functionalization of ZnO Nanoparticles by Glutamic Acid and Conjugation with Thiosemicarbazide Alters Expression of Efflux Pump Genes in Multiple Drug-Resistant Staphylococcus aureus Strains. Microb. Drug Resist. 2019, 25, 966–974. [Google Scholar] [CrossRef] [Scilit]
- Djearamane, S.; Loh, Z.C.; Lee, J.J.; Wong, L.S.; Rajamani, R.; Luque, P.A.; Gupta, P.K.; Liang, S.X.T. Remedial Aspect of Zinc Oxide Nanoparticles Against Serratia Marcescens and Enterococcus Faecalis. Front. Pharmacol. 2022, 13, 891304. [Google Scholar] [CrossRef] [Scilit]
- Premanathan, M.; Karthikeyan, K.; Jeyasubramanian, K.; Manivannan, G. Selective Toxicity of ZnO Nanoparticles toward Gram-Positive Bacteria and Cancer Cells by Apoptosis through Lipid Peroxidation. Nanomedicine 2011, 7, 184–192. [Google Scholar] [CrossRef] [Scilit]
- Elabbasy, M.T.; El Bayomi, R.M.; Abdelkarim, E.A.; Hafez, A.E.S.E.; Othman, M.S.; Ghoniem, M.E.; Samak, M.A.; Alshammari, M.H.; Almarshadi, F.A.; Elsamahy, T.; et al. Antibacterial and Antibiofilm Activity of Green-Synthesized Zinc Oxide Nanoparticles Against Multidrug-Resistant Escherichia Coli Isolated from Retail Fish. Molecules 2025, 30, 768. [Google Scholar] [CrossRef] [Scilit]
- Chauhan, R.; Reddy, A.; Abraham, J. Biosynthesis of Silver and Zinc Oxide Nanoparticles Using Pichia Fermentans JA2 and Their Antimicrobial Property. Appl. Nanosci. 2015, 5, 63–71. [Google Scholar] [CrossRef] [Scilit]
- Ravi, J.; Gunasekar, B.; Basha, J. Synergistic Antimicrobial Activity of Colistin and Amikacin with Zinc Oxide Nanoparticles and Their Posttranscriptional Regulation of Mcr-1 Gene Expression in Colistin-Resistant Klebsiella Pneumoniae. Microb. Drug Resist. 2025, 31, 201–210. [Google Scholar] [CrossRef] [Scilit]
- Ghasemi, F.; Jalal, R. Antimicrobial Action of Zinc Oxide Nanoparticles in Combination with Ciprofloxacin and Ceftazidime against Multidrug-Resistant Acinetobacter Baumannii. J. Glob. Antimicrob. Resist. 2016, 6, 118–122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raghupathi, K.R.; Koodali, R.T.; Manna, A.C. Size-Dependent Bacterial Growth Inhibition and Mechanism of Antibacterial Activity of Zinc Oxide Nanoparticles. Langmuir 2011, 27, 4020–4028. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heidary, M.; Bostanabad, S.Z.; Amini, S.M.; Jafari, A.; Nobar, M.G.; Ghodousi, A.; Kamalzadeh, M.; Darban-sarokhalil, D. The Anti-Mycobacterial Activity of Ag, ZnO, and Ag-ZnO Nanoparticles Against MDR- and XDR-Mycobacterium Tuberculosis. Infect. Drug. Resist. 2019, 12, 3425–3435. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Geng, S.J.; Hao, P.F.; Wang, D.; Zhong, P.; Tian, F.; Zhang, R.; Qiao, J.; Qiu, X.; Bao, P. Zinc Oxide Nanoparticles Have Biphasic Roles on Mycobacterium-Induced Inflammation by Activating Autophagy and Ferroptosis Mechanisms in Infected Macrophages. Microb. Pathog. 2023, 180, 106132. [Google Scholar] [CrossRef] [Scilit]
- Jafari, A.; Jafari Nodooshan, S.; Safarkar, R.; Movahedzadeh, F.; Mosavari, N.; Novin Kashani, A.; Dehghanpour, M.; Kamalzadeh, M.; Rasouli Koohi, S.; Fathizadeh, S.; et al. Toxicity Effects of AgZnO Nanoparticles and Rifampicin on Mycobacterium Tuberculosis into the Macrophage. J. Basic. Microbiol. 2018, 58, 41–51. [Google Scholar] [CrossRef] [Scilit]
- Gominet, M.; Compain, F.; Beloin, C.; Lebeaux, D. Central Venous Catheters and Biofilms: Where Do We Stand in 2017? APMIS 2017, 125, 365–375. [Google Scholar] [CrossRef] [Scilit]
- Mermel, L.A.; Allon, M.; Bouza, E.; Craven, D.E.; Flynn, P.; O’Grady, N.P.; Raad, I.I.; Rijnders, B.J.A.; Sherertz, R.J.; Warren, D.K. Clinical Practice Guidelines for the Diagnosis and Management of Intravascular Catheter-Related Infection: 2009 Update by the Infectious Diseases Society of America. Clin. Infect. Dis. 2009, 49, 1–45. [Google Scholar] [CrossRef] [Scilit]
- O’Grady, N.P.; Alexander, M.; Burns, L.A.; Dellinger, E.P.; Garland, J.; Heard, S.O.; Lipsett, P.A.; Masur, H.; Mermel, L.A.; Pearson, M.L.; et al. Guidelines for the Prevention of Intravascular Catheter-Related Infections. Clin. Infect. Dis. 2011, 52, e162–e193. [Google Scholar] [CrossRef] [Scilit]
- Karlowicz, M.G.; Hashimoto, L.N.; Kelly, R.E.; Buescher, E.S. Should Central Venous Catheters Be Removed as Soon as Candidemia Is Detected in Neonates? Pediatrics 2000, 106, E63. [Google Scholar] [CrossRef] [Scilit]
- Hajipour, M.J.; Fromm, K.M.; Akbar Ashkarran, A.; Jimenez de Aberasturi, D.; de Larramendi, I.R.; Rojo, T.; Serpooshan, V.; Parak, W.J.; Mahmoudi, M. Antibacterial Properties of Nanoparticles. Trends Biotechnol. 2012, 30, 499–511. [Google Scholar] [CrossRef] [Scilit]
- Abdelghafar, A.; Yousef, N.; Askoura, M. Zinc Oxide Nanoparticles Reduce Biofilm Formation, Synergize Antibiotics Action and Attenuate Staphylococcus aureus Virulence in Host; an Important Message to Clinicians. BMC Microbiol. 2022, 22, 244. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMAScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]






Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.