


Abstract
Background: Coverage rates of routinely recommended vaccines in older adults still fall below the targets established by international and national advisory committees. As a result, related diseases still have a high incidence, morbidity, and mortality. Information and Communication Technologies (ICT) could provide useful tools to improve immunization rates by bringing information directly to the target user at a relatively low cost. The present research aims to systematically review recent literature on interventions applying ICT to improve the uptake of influenza, pneumococcal, COVID-19 and herpes zoster immunization rates among older adults. Methods: Studies published in English between 1 January 2000 and 10 November 2022 were identified by searching electronic medical databases (PubMed, Scopus) and were independently reviewed by two different authors. A total of 22 studies were included in this review. Findings: Interventions applied the following ICT tools: phone calls, text messages, messages sent via personal electronic medical records, automated phone calls, remote patient monitoring in a home telehealth program and emails. In terms of the vaccines promoted, 11 studies prompted the influenza vaccine, four prompted the influenza and pneumococcal vaccines, three the pneumococcal vaccine, two the herpes zoster vaccine, one the COVID-19 vaccine and one both the pneumococcal and herpes zoster vaccines. Overall, more than half of the studies (n = 12) found some level of effectiveness of these ICT strategies in increasing vaccination rates among older adults, while five studies were partially effective (for specific vaccines or population subgroups), and five reported no significant effect. Conclusions: Prevention programs using ICT tools could be effective in promoting immunizations among older adults.
1. Introduction
Increasing and maintaining vaccination coverage is of fundamental importance to further decreasing the burden of vaccine-preventable diseases and thus has been identified as a public health priority [1,2]. Despite recommendations, immunization rates among individuals aged 65 years and older are generally low. Estimates of vaccination coverage in the United States in 2019 for three key adult vaccines—influenza, pneumococcal disease, and herpes zoster (HZ)—ranged from 41.2% for the HZ vaccine to 70.5% for the influenza vaccine [3]. Similarly, vaccination rates among the elderly in other high-income countries remain insufficient despite the availability of vaccines and despite convincing evidence-based medical and economic rationales. For example, data from the 2016–2017 influenza season showed that influenza vaccination coverage rates in European countries ranged from 2% to 72.8%, with a median of 47.1%; the highest vaccination coverage rates were recorded by the UK, which almost reached the European target of 75% [4]. European pneumococcal vaccination coverage among older adults is even lower, reaching 24.2% [5].
As a consequence, the burden of vaccine-preventable diseases remains high in older adults, contributing to substantial morbidity, mortality, and healthcare resource use and costs [6,7,8]. Older adults, together with people with chronic diseases (e.g., cancer patients), represent the population subgroup that would benefit most from vaccination, as they are at risk of developing serious complications. It has been estimated that between 70% and 85% of recent seasonal flu-related deaths have occurred in people 65 years and older, and that 50% to 70% of seasonal flu-related hospitalizations have also occurred among people in this age group [9].
Suboptimal vaccination coverage results from a variety of challenges and obstacles, not just the spread of vaccination hesitancy in the general population and the increased hesitancy of providers to vaccinate themselves and to recommend vaccination for their patients [10,11], but also from a lack of communication. Indeed, factors often associated with non-adoption of vaccination are the absence of awareness of the need for and importance of vaccination and the lack of vaccine recommendation by healthcare professionals [10]; the key points for effective immunization programs in the elderly are all related to patient contact and communication: improving access to vaccination, reminding patients of vaccination appointments, and increasing patient awareness of the importance of vaccination [12].
Immunization campaigns can be supported by different sources of Information and Communication Technologies (ICT) that can potentially bring information directly to the individuals. Although there is no single, universal definition of ICT, the term is generally accepted to refer to all devices, network components, applications and systems that, combined, enable people and organizations to interact in the digital world. ICT encompasses both the interconnected and mobile spheres powered by wireless networks. It also includes antiquated technologies, such as fixed telephony, which are still widely used today.
Technology offers new and creative methods to address vaccination barriers for families, health care providers, and the broader community, due to its prevalence in society and its flexibility [13]. Since 2005, the World Health Organization has urged member states “to develop the infrastructure for [ICT] for health as deemed appropriate to promote equitable, affordable, and universal access to their benefits, and to continue to work with information and telecommunication agencies and other partners in order to reduce costs and make eHealth successful” [14].
Technology use in high-income countries is widespread: the vast majority (92%) of people aged 65 years or older in the United States own a cell phone [15], and this is paralleled by the widespread use of the internet, social media, and email, which creates other promising routes for health communication [13]. In addition to consumer use of technology, healthcare providers are being incentivized to integrate technology into their practice: Coronavirus disease 2019 (COVID-19) accelerated the global adoption of telemedicine [16], and healthcare organizations increasingly offer patients access to their personal electronic health records (EHR) to manage their health [17]. The combination of EHR use, the growing number of immunization registries, and the resulting ability to have vaccination data in electronic form provides an important foundation for delivering ICT-based vaccine interventions [13].
Finally, ICT can offer a cost-effective and accessible way to promote immunizations as an alternative to the traditional means of communication (e.g., letters) or the engagement of health care professionals [18,19].
While previous systematic reviews have assessed the effect of immunization programs [20,21,22,23,24], including technology-based programs [25,26], to the best of our knowledge, no review has specifically focused on ICT use in the older adult population.
The aim of this systematic review is to evaluate recent literature on interventions that apply ICT to improve the uptake of the influenza, pneumococcal, COVID-19, and herpes zoster vaccines among older adults.
2. Methods
The review methods were defined in advance, following the Prepared Items for Systematic Reviews and Meta-Analysis (PRISMA) guidelines [27]. Studies were included in the review if they met the following criteria:
- (a)
- Were focused on increasing at least one of the universally recommended vaccinations for older adult populations in high-income settings: the pneumococcal vaccine, the seasonal influenza vaccine, the herpes zoster vaccine, or the COVID-19 vaccine [2].
- (b)
- Investigated the use of an ICT-based intervention to increase vaccination coverage.
- (c)
- Included participants over 60 years old.
- (d)
- Were original studies using a before-and-after, quasi-experimental, or experimental study design (i.e., guidelines, reviews, letters, and editorials were excluded).
- (e)
- Were published from 1 January 2000 to 10 November 2022.
- (f)
- Were written in English.
- (g)
- This systematic review does not include studies involving specific vaccinations delivered exclusively to subgroups of older adults, such as people with specific medical conditions (e.g., the Hemophilus vaccine for splenectomy patients) or international travelers.
2.1. Search Strategy
The electronic databases Pubmed and Scopus were used to find original studies. The reference lists of reviews that were found during the search were also hand-searched for relevant studies.
The search strategy was built using a combination of keywords for the 4 main axes of our research question: (1) the selected target population (older adults), (2) the selected interventions (those applying ICT strategies), (3) the selected vaccinations (universally recommended vaccines for older adults), (4) the selected outcome (evaluation of immunization rates). Within each axis, we combined keywords with the “OR” operator and we then linked the search strategies for the two axes with the “AND” operator. The search strings are reported in Appendix A.
2.2. Study Selection and Data Extraction
Identified studies were independently reviewed for eligibility by two authors (GG, MT) in a two-step-based process: an initial screen was performed based on title and abstract, then full texts were retrieved for a second screen. At both stages, disagreements between the two reviewers were resolved by consensus or by consulting another author (AB).
A data extraction form based on the research question was developed in Microsoft Excel. Data were collected on the following study characteristics: (1) author name, year, and country of publication; (2) study design; (3) study setting, study period and study population; (4) vaccines considered; (5) the type of ICT applied; (6) the intervention description and aims; (7) outcomes of interest; and (8) author conclusions.
We performed descriptive analysis to report the characteristics of the included studies. To summarize the findings on the effectiveness of each intervention across multiple studies, we displayed the results of individual studies. If unadjusted and adjusted outcomes were available, we recorded the adjusted estimates to reduce confounding factors.
2.3. Quality Assessment
The two authors that reviewed the retrieved studies for eligibility (GG, MT) also independently assessed the quality of selected studies using the Cochrane Risk of Bias 2.0 (RoB 2) tool [28] for RCT, the Risk Of Bias In Non-randomized Studies—of Interventions (ROBINS-I) [29] for non-randomized trials, and the National Institutes of Health (NIH) quality assessment tool for before–after (Pre–Post) studies with no control group [30]. Reviewer disagreements were resolved by consensus or by consulting a third author (AB). Appendix B shows the quality assessment assigned to each study.
3. Results
3.1. Identified Studies
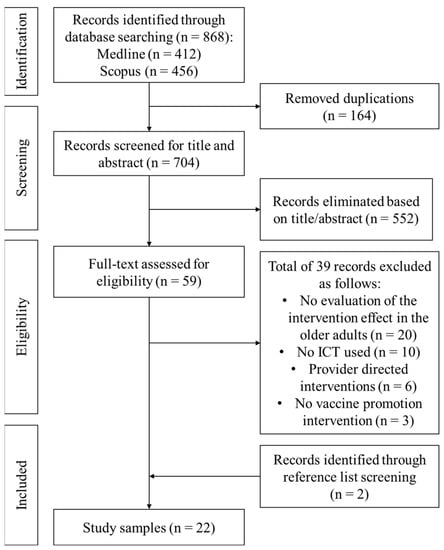
The research strategy returned a total of 868 citations from electronic databases. After removal of duplicates, 704 titles and abstracts were screened and 59 full texts were assessed for eligibility, 20 of which met the exclusion and inclusion criteria. Two additional relevant studies were identified by screening the reference lists of previous reviews, resulting in a total of 22 articles included in this systematic review (Figure 1).
Figure 1.
The Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) diagram of the article search.
3.2. Characteristics of the Included Studies
Major characteristics of the studies identified and included in our review are reported in Table 1. Table 2 shows the results of these retrieved studies.
Table 1.
Overview of included studies: characteristics, materials and methods.
Table 2.
Overview of included studies: results.
The majority of the studies (n = 15) were conducted in the United States [19,32,35,36,37,38,39,41,43,45,46,47,48,49,50], three around Europe (Spain [42], the UK [34], France/Monaco [44]), two in the Middle East (Lebanon [33] and Turkey [31]), one in Canada [40], and one in Australia [18].
In terms of the study designs, most interventions (n = 15) were Randomized Controlled Trials (RCT) [18,19,34,35,37,38,39,41,43,44,45,46,48,49], while the others either had a quasi-experimental design [31,36,42] or were before-and-after trials [32,40,47,50].
Almost all interventions involved the general population with the exception of four studies that focused on individuals suffering from specific clinical conditions: asthma or chronic obstructive pulmonary disease [37], patients diagnosed with a selected rare disease [42], patients in a home telehealth program with selected characteristics in terms of clinical issues, dependencies in activities of daily living and social support network [50] or patients with hypertension [39].
Of the 22 included studies, 11 promoted the influenza vaccine [18,34,35,36,39,40,42,43,45,46,50], four promoted both the influenza and the pneumococcus vaccines [37,38,44,48], three the pneumococcus vaccine [31,33,41], one the COVID-19 vaccine [32], two the herpes zoster vaccine [19,47] and one both the pneumococcal and the herpes zoster vaccines [49].
All but one of the studies reported results on vaccine coverage, while only one study [40] exclusively assessed the willingness of people to get immunized. One other study [41] evaluated both outcomes.
Some of the included ICT-based interventions also incorporated the patients’ personal catchment conducted with a traditional method of communication (i.e., postcards, letters, or informational sheets) as follows: (a) in three studies [34,36,44], the entire population (controls and interventions) received a personal catchment with traditional means of communication as well as an ICT-based contact, which was conducted only in the intervention group; (b) in seven studies [30,31,32,34,39,41,42], the personal catchment was conducted only in the intervention group using both ICT strategies and traditional means of communication (with no personal contact in the control group); (c) four studies [19,31,37,39] compared the effects of an ICT-based intervention with an intervention using exclusively traditional means of communication.
A health education component (i.e., a message about the importance and safety of the investigated vaccine) was included in 11 out of the 22 studies [19,31,32,33,38,39,40,41,44,45,50], while the others used an ICT tool merely as a vaccination reminder [18,31,34,36,37,42,43,46,47,48,49].
The following ICT tools were used in the studies investigated: 10 interventions were conducted by telephone calls [31,32,34,35,36,37,38,39,40,41], four used text messages [18,42,43,44], three sent messages via electronic health systems [19,45,46], three used autodial calls [47,48,49] and remote patient monitoring in a home telehealth program [50], and one study included a mix of tools (telephone calls, text messages, and emails) in different subgroups [33].
3.3. Telephone Calls
Among the 10 intervention studies conducted by means of telephone calls, six were RCTs [32,35,36,38,41,46], two were non-RCTs [34,49] and two were before-and-after studies [31,50]. Among the controlled studies, six out of eight showed a good level of efficacy, with vaccination rates in the intervention group exceeding those in the control group by 6.3 to 42 percentage points [32,36,38,41,46,49]. With regard to the two before-and-after studies, one of them was effective in increasing vaccination rates by 40 percentage points [50], while the other had a very small effect (three new patients vaccinated out of 59) [31].
Telephone calls were applied in two different kinds of interventions: (a) dialogue-based interventions with a relevant educational component, and (b) patient reminders or invitations to schedule an immunization appointment.
- (a)
- Dialogue-based interventions with an educational component.
Among the studies conducted with telephone calls, six out of 11 offered a dialogue-based intervention with a relevant health educational component that provided information about the importance and safety of the vaccine and assessed participants’ main concerns [31,32,38,39,40,41]. Three of these were RCT [38,39,41] and all saw higher immunization rates in the intervention groups compared to control groups.
In particular, Krieger et al. [38] aimed at increasing pneumococcal and influenza immunization rates among urban seniors using peer-to-peer outreach. The intervention group received educational brochures in the mail and was contacted by volunteers to encourage immunization and address specific barriers, while the control group was exposed to the usual senior/community immunization promotion activities. The intervention was effective, particularly in increasing pneumococcal immunization rates (intervention group: 52.0%, 95% CI [46.6–57.4]; control group: 30.9%, 95% CI [26.6–35.2]; rate ratio = 1.68, 95% CI [1.40–2.03]). The intervention was also effective for influenza vaccination among those that were not immunized in the previous year (intervention group: 50.0%, 95% CI [40.0–60.0]; control group: 23.0%, 95% CI [15.2–33.3]; rate ratio = 2.17, 95% CI [1.42–3.31]), while the rate ratio was lower among those that were immunized in the prior year but remained significant (rate ratio = 1.04, 95% CI [1.01–1.07]).
Winston et al. [41] evaluated the effectiveness of adding a telephone intervention conducted by a nurse (just in the intervention group) to a pre-existing reminder letter (received by both interventions and controls) with the goal of increasing pneumococcal vaccination in a target population. The added contact by phone was successful at increasing vaccination rates, with 17% (201/1198) of the intervention patients being vaccinated versus 8% (100/1197) of the controls, at 6-month follow-up.
Minor et al. [39] evaluated the effectiveness of both mail (first intervention group) and telephone (second intervention group) communication strategies, comparing them to a control group (which received standard clinical approaches). This was conducted with patients of a hypertension clinic and was aimed at improving existing influenza vaccination rates among those not seeking early seasonal vaccination. Both the intervention groups were more effective than the control, with the phone group resulting in higher vaccination rates (females: control group 50.0%, mail 54.4%, phone: 58.9%; males: control group 58.3%, mail 58.3%, phone 87.5%).
Three telephone-based interventions with an education component had a pre–post intervention design [32,33,40]. Desir et al. [32] reported a tailored, dialogue-based intervention aimed at increasing COVID-19 immunizations in older adults in an outpatient geriatric clinic who were identified as possibly not having been vaccinated in the summer and fall of 2021 (information from electronic medical records). The interventions provided relevant information and/or logistical assistance. Of 59 non-vaccinated older adults, the patients who had expressed interest in vaccination (n = 20) were re-contacted approximately 1 month later to ask about their updated vaccination status: as a result, four (6.8%) received the COVID-19 vaccination at the end of the intervention.
Strain et al. [40] reported a telephone script-based intervention created to guide a brief (1–3 min) discussion on influenza vaccination between pharmacy staff and unvaccinated individuals. This was conducted predominantly at the “tail end” of the vaccination season, in order to target those who did not respond to initial invitations from their primary care physicians. The main outcome of the study was for contacted individuals to have a vaccine administration appointment arranged by the end of the phone consultation (i.e., showing willingness to get immunized). Among 474 individuals that did not have documented influenza vaccination, 316 (67%) agreed to receive the vaccine by the end of the consultation [40].
Ghadieh et al. [33] looked at pneumococcal immunizations, analyzing the effect of three different types of patient reminder system (short phone calls, text messages, and e-mails), with the addition of a brief education intervention about the seriousness of pneumococcal disease in half of the subgroups (for a total of six intervention subgroups). Each subgroup received three identical reminders given at four-week intervals, in which patients were asked to call the clinic themselves and schedule an appointment to receive the vaccine. The rates of vaccination in patients older than 65 years increased from 17.2% to 20.4% before and after the intervention, but the study did not provide any specific data comparing the intervention subgroups to a historical control. The authors reported that telephone calls have a greater impact than email or SMS in the overall sample (which also included younger adults), and that all intervention groups have better results than the control group (i.e., no intervention). There was also no statistical significance when stratifying the results according to age.
Lastly, Biyik et al. [31] conducted a quasi-experimental study assessing the impact of doctor recommendations through face-to-face interviews (for patients who attended a family health center, n = 103 patients) or by phone (for patients who did not attend the clinic, n = 97 patients) on pneumococcal vaccination rates. They reported that 59.8% of patients contacted by telephone received the vaccine versus 81.6% of those that were interviewed face-to-face.
- (b)
- Patient reminders/recalling and invitations to schedule an appointment to get immunized.
Four studies (three RCT [34,35,37] and one non-RCT [36]) contacted individuals by telephone, inviting them to schedule an immunization appointment or reminding them about the opportunity to receive a certain vaccine. Three studies focused on influenza immunization [34,35,36] and one on both the influenza and pneumococcal vaccines [37]. Two of these studies reported higher immunization rates in the intervention group than in the control group [34,35].
Humiston et al. [35] provided a multicomponent intervention based on: (1) GP reminders, (2) patient recalling (mailed influenza immunization reminders in the form of a letter or card), and (3) patient outreach (phoning patients who had no routine appointment scheduled during the 3-month flu vaccine period and asking them to make an appointment). Patients in the intervention group were more than six times more likely to be vaccinated than patients in the control group (odds ratio = 6.25, 95% CI [5.41–7.22], p = 0.0001).
Hull et al. [34] reported an intervention directed at low-risk patients aged 65 to 74 years who had not previously been in a recall system for influenza immunization. The intervention was based on a telephone call from the receptionist, offering an appointment to receive the vaccine. With this, immunization rates were boosted by about 6.3% (p = 0.026).
On the other hand, some studies found no effect of these interventions. For instance, Kellerman et al. [36] conducted an intervention on non-responders from a family practice center that had already received a postcard urging influenza immunization in the previous month. The intervention group was contacted by phone but no significant increase in immunization rates was found compared to the controls.
Similarly, Klassing et al. [37] looked at influenza and pneumococcus immunization rates, comparing the effect of pharmacy-initiated interventions directed at asthma or COPD patients. Patients were randomized into one of the three study arms: phone calls, mailed letters, and controls. No significant difference was found between the interventions and the control group for the over-65 population.
3.4. Text Messages
The four interventions that applied text messages were three RCTs [18,43,44] and one non-RCT [42]. Three of these exclusively used text messages to invite/remind patients to get immunized against influenza, without any other traditional means of communication and without offering any kind of health education program [18,42,43]. Of these, one RCT increased vaccination rates by five percentage points compared to controls [18], two were only partially effective because they increased vaccination coverage only in specific population subgroups or only for certain vaccinations [45,47], and one had no significant effect [37].
Two of these studies were conducted in primary care settings [18,43]. Regan et al. [18] found that the use of an SMS reminder, sent 6 weeks after the influenza season began, increased vaccination rates by 5% for patients 65 years of age or older (20.5% vaccinated, n = 376 in the intervention group vs. 15.8% vaccinated, n = 281 in the control group, RR = 1.26, 95% CI [1.10–1.45], p < 0.05). Patel et al. [43] also evaluated the effect of text messaging: 19 different protocols (nudges) were developed by behavioral scientists to boost influenza vaccination rates during routine primary care visits; nudges varied in their message contents and/or timing (up to two sets of messages were sent from the patient’s healthcare provider in the 3 days preceding the patient’s appointment). Although some nudge protocols were effective among the overall population of the study, and the subgroups analysis by patient age showed no significant differences among the age subgroups, none of the nudge protocols was significantly effective among the patients aged 65 years of age or older. The third study was conducted by Esteban-Vasallo et al. [42], assessing the effect of text message reminders on influenza vaccination uptake in patients with selected rare diseases and delayed vaccination status. The authors found that, for older adults, the reminder was associated with a significantly higher vaccination probability in patients that had at least one concurrent chronic condition in addition to the rare disease (IRR = 1.23, CI 95% [1.08–1.40]). When further analyzing by sex, the authors report that the intervention was effective for men with at least one concurrent chronic condition in addition to the rare disease (IRR: 1.58, CI 95% [1.25–2.00]) and for women without concurrent chronic conditions (IRR: 1.40, CI 95% [1.05–1.89]). Lastly, Tubiana et al. [44] reported a multifaceted intervention aimed at increasing pneumococcal and influenza vaccination rates in patients aged 65 years and older that had gone to an Emergency Department. Patients in the experimental group received a brief structured interview with the physician about issues associated with pneumococcal and influenza infections and the importance of both vaccinations. They were also given an information sheet with an explanation about the risks and benefits of vaccination and a letter dedicated to the general practitioner stating that the patient was at risk for pneumococcal infection and could benefit from pneumococcal vaccination. In addition, three text messages were sent to the patients every 2 weeks to remind them to talk about pneumococcal risks with their general practitioners. Patients in the control group had a similar intervention, except that they did not receive the text message reminders and they had a non-structured interview about pneumococcal risks and vaccination. The primary outcome was self-reported pneumococcal vaccination within 6 months, with 6-month self-reported influenza vaccination being evaluated as a secondary outcome. In the intention-to-treat analysis, the intervention did not alter the pneumococcal vaccination rate (6.4% vs. 4.6%, absolute difference: 1.8, 95% CI [−0.9–4.4], p = 0.19), but it did improve the influenza vaccination rate (52.1% vs. 40.0%, absolute difference: 12.1, 95% CI [2.4–21.8], p = 0.01).
3.5. Automated Phone Calls
Three interventions used automated phone calls: two of them were RCTs [48,49], and one had a before-and-after design [47]. One of the RCTs increased vaccination rates in the intervention group by 1.5 percentage points compared to the control group [33], while the other had no significant effect [43]; the before-and-after study showed a higher number of vaccinations during the intervention period compared to the control period (25 vs. 16) [42].
Hurley et al., conducted a RCT using auto-dial calls as centralized patient reminders/recalls to increase seasonal influenza, pneumococcal, and Tdap vaccines (not considered in this review) [48]. Over 3–4 months, participants received up to two auto-dial phone calls followed by a postcard indicating that they may need one or more vaccines (without specifying what vaccines were needed), encouraging them to schedule an appointment or to go to a pharmacy and get immunized. The intervention was effective in increasing influenza vaccination in older adults, with 32.0% (n = 847) receiving a vaccine in the intervention group versus 28.6% (n = 760) in the regular-care group (p < 0.01). No significant difference was found for the pneumococcus vaccine.
The other RCT, conducted by Stolpe et al. [49], found no significant increase in pneumococcal and herpes zoster vaccination rates among community pharmacy patients who received an automated telephone call offering the vaccines compared with control group patients who received a scheduled outbound communication without the added vaccination prompt.
Also aiming to promote herpes zoster vaccine among patients of a community pharmacy, Bedwick et al. found, in a before-and-after trial [47], that a total of 25 herpes zoster vaccines were administrated during the intervention period, compared with 16 administrated during the same period in the previous year.
3.6. Personal Electronic Health Records
Three of the RCTs were conducted using EHR [19,45,46]. One of them increased vaccination rates in the intervention group by eight percentage points compared to the control group [19], while the others had no effect or showed only small significant improvements in a specific sub-analysis [39,40]. Otsuka et al. [19] included patients from a general internal medicine clinic aged 60 years and older, assessing the effect of giving an informational packet (regarding shingles and the herpes zoster vaccine) through EHR or through the national postal service, comparing their standard of care. At their 6-month follow-up, both strategies were effective in increasing vaccination rates compared to the controls (relative risk for the EHR group: 2.7, 95% CI [1.6–4.5], p = 0.0001; relative risk in the non-EHR group: 2.9, 95% CI [1.6–5.5], p = 0.0007) and the outcome of the logistic regression interaction likelihood ratio test revealed that the effects of the two interventions were not significantly different (p = 0.99).
The other two interventions using EHR were conducted by Szilagyi et al. in 2020 [45] and 2022 [46]. Both studies aimed at increasing influenza vaccination rates using messages sent via the healthcare system’s EHR, where the first study provided relevant information about vaccine safety and effectiveness [45], and the second used messages tailored to patient characteristics (i.e., age and any chronic diseases) and incorporated behavioral science strategies [46]. The primary outcome of both studies was to register influenza vaccination in the EHR after the intervention, while the secondary outcome also included self-reported vaccination by the patients in response to a portal reminder (this option was only available for the intervention group). Both studies found no significant effect on the primary outcome, but when self-reported vaccination was taken into account, the first study found a significant improvement in vaccination rates with a dose–response increase depending on the number of reminders sent (vaccination rates: 53.6% in the control group, 54.6% in the one-reminder group, 55.1% in the two-reminder group, and 56.7% in the three-reminder group; p < 0.001) [45]. In the second study, no significant difference was noted in influenza vaccination rates, but adjusted multivariate analyses showed a small effect for the “loss frame” behavioral science strategy (in which the message describes what a person has to lose by taking a particular action; RR = 1.03, 95% CI [1.01–1.05], p < 0.01) [46].
3.7. Remote Patient Monitoring in a Home Telehealth Program
One study with a before-and-after design aimed to improve seasonal influenza vaccine rates among patients with specific clinical issues, dependencies in activities of daily living, or a poor social support network who were part of a home telehealth program [43]. Automated two-way messaging offering the influenza vaccination was transmitted using remote patient monitoring, and tailored education was provided during a telephone visit for patients that had no vaccination plans. As a result, 81.7% of patients aged 66 years and older received the vaccine during the intervention period, but the intervention was insignificant in increasing vaccination rates compared with the previous flu season (control period).
4. Discussion
This systematic review summarizes the data from ICT-based interventions aimed at increasing immunization rates for recommended vaccines in older adults. The 22 retrieved studies are heterogenous in terms of the included populations (i.e., some focus on the general population while others focus on individuals suffering from a specific disease or vaccine-hesitant individuals) and are also heterogenous in terms of the intervention strategies (i.e., simple reminders/recalls, educational interventions, traditional means of communication in addition to the ICT tool, or multicomponent interventions).
Overall, half of the included studies (n = 12) found some level of effectiveness of ICT strategies in increasing vaccination rates among older adults [18,19,31,33,34,35,38,39,40,41,47,48]. In particular, higher effects were found in one study that used patient recall and provider prompts, leading the intervention group to be more than six times as likely to receive the influenza vaccine [35]. The highest effect of this intervention is probably due to its multi-component approach (mailed reminders for flu immunization plus up to two phone calls to patients who had not scheduled a routine appointment) and the high level of GP engagement through the reminders (patients’ charts were marked with a reminder to the doctor that the patient had not been vaccinated).
Another intervention using telephone contacts plus educational brochures mailed to the participants greatly increased both influenza (50.0% intervention vs. 23.0% control) and pneumococcal (52.0% intervention vs. 30.9% control) immunization rates [38]. It is worth noting that interventions using leaner ICT strategies (such as electronic messages or autodial calls) that cost less in terms of time and human resources found good levels of effectiveness. For instance, Regan et al. [18] and Otsuka et al. [19] found a respective 5% and 8% improvement in vaccination rates in the intervention groups compared to controls.
Other interventions (n = 5) were only partially effective, finding an increase in immunization rates only for specific vaccines or for population subgroups [32,42,44,45,46]. One example is a multicomponent intervention with a consistent educational component that revealed that text message reminders were effective in increasing influenza but not pneumococcal vaccination rates [44]. It should be noted that this study enrolled patients visiting an emergency department after their acute medical condition was resolved; thus, they could have been reluctant and not so interested in the prevention program. Furthermore, awareness of the need to recommend pneumococcal vaccination is probably lower among both physicians and patients than for the influenza vaccine [51]. Other authors have also reported that external factors may hamper pneumococcal vaccination, such as problems in pneumococcal vaccine supply [44]. Two other studies that were partially effective were conducted by the same authors, in a similar population, using EHRs over two consecutive different years (2018–2019 and 2019–2020) [45,46]. One possible reason for the lack of impact in these studies is that not all the patients opened the portal messages, so perhaps strategies that encourage patients to read these reminders might be helpful. Another included study was successful in implementing vaccination rates by using EHR messages [19]; however, further studies are needed to clarify the role of this technology in vaccination promotion. Similarly, another partially effective study [42] aimed at increasing influenza immunization using text messages (in this case, patients had certain rare diseases as well as delayed vaccination) and found that receiving the reminder was associated with a significantly higher probability of vaccination in patients with at least one concurrent chronic condition in addition to their rare disease. This higher vaccination uptake could be related to a higher perception of risk, as well as more frequent contact with health facilities, thus increasing the opportunities for vaccination. Although the intervention was only modestly effective, the authors suggest that it might be a good additional strategy to improve vaccine uptake, since it is simple, feasible, affordable, and easily scalable, particularly when immunization and target population data are available in digital registries.
Lastly, five studies found no significant effect of the intervention [36,37,43,49,50]; these interventions varied in terms of the technology used, which included text messaging, phone calls and automated phone calls. One non-effective telephone-based study focused on non-responder patients of a family practice that had already received a mailed invite to get immunized against influenza the month before [36]. In this case, the lack of an effect is likely to be influenced by the previous mail-based intervention—this being effective, it would have left a population of individuals that were more hesitant towards the vaccine, probably less aware of influenza risks, and generally less motivated to be immunized, meaning that they were not influenced by the intervention. Also, an educational intervention conducted on home telehealth patients revealed no significant improvement on influenza vaccination rates compared with the previous flu season: however, it is important to note that vaccination rates among this particularly frail population were already quite high, with more than 80% of older adults vaccinated [50].
Another non-effective study was a telephone-based pharmacist-initiated three-arm trial focusing on individuals suffering from asthma or chronic obstructive pulmonary disease [37]. The sub-analysis conducted for patients over 65 years of age found no significant difference in pneumococcal and influenza vaccine rates between the two intervention arms (a phone call and a mailed letter) and the control group. This study saw a high vaccination rate within the control group that may have come from a high baseline level of vaccination within the pharmacy populations, largely due to both the socioeconomic status of the study participants, and the high number of vaccination advertisements during the study time period [37]. In each of the three involved pharmacies, printed advertisements promoting in-store immunizations were given with each prescription for the duration of the study period and a new CDC recommendation for the pneumococcal vaccine was released during the same period, which was highly publicized in print and on TV. Furthermore, during the course of the phone call intervention, many patients expressed the desire to discuss the vaccine recommendations at their next physician appointment (after the conclusion of the study period), suggesting that patients in the letter group may have had this same idea [37]. Another intervention using automated calls to improve pneumococcal and herpes zoster vaccines revealed low call completion rates, with 28.2%, 6.2% and 1.0% of call attempts completed for the first, second and third attempts, respectively, which is probably the main reason for the inefficacy of the intervention itself [49]. Finally, a study prompting influenza immunization using 19 different text messaging (nudges) protocols found that none of them was effective in increasing vaccination rates among older adults, although some were effective among the overall population, and subgroups analysis by patients’ age showed no significant difference between the older and the younger groups [43]. In addition, because a previously published interim analysis of the same study, reporting only data of patients enrolled in the fall of 2020, showed a higher overall effect among the overall population and a significant effect of a nudge protocol among older adults [52], the authors hypothesized that the release of the COVID-19 vaccine that began in January 2021 may have influenced influenza vaccination rates in the trial.
The acceptance and rejection of vaccines is highly context-dependent and is influenced by ‘local vaccine cultures’, social, cultural, historical and political factors [53]. Most of the studies included in this review were conducted in countries that offer free or insured vaccines for the elderly population, and the lack of an economic barrier probably improves vaccination uptake. This is supported by the results of one of the included studies [47], in which both pneumococcal and influenza vaccination were promoted, but the intervention was only effective for the influenza vaccine, which was the only one offered free of charge. On the other hand, it is worth noting that the only study in which the vaccine was paid for out of pocket by the participants also proved effective [48]; this could be explained by the fact that it was conducted in a middle-income country in which vaccine acceptance is generally high, mainly due to an increased interest in personal protection against infectious diseases and trust in health professionals as sources of guidance [54]. In addition, the setting of the vaccination service and/or vaccine promotion activity could influence vaccination uptake; for example, this review included five studies in which the vaccine promotion intervention was based on telephone calls [35,38,50] or automated calls [42,43] and conducted by pharmacists; three of these were found to be effective in increasing vaccination rates, a slightly higher rate of effectiveness than that found in interventions conducted in primary care centers (six out of 11 effective studies). Despite the low number of studies and the need for further research, community pharmacies could contribute to achieving vaccination goals by increasing vaccination rates due to their multiple locations in metropolitan and urban areas, convenience, extended opening hours and reduced costs for vaccine administration [55].
Despite the use of ICT communication methods, which are particularly novel when considering non-telephone-based studies, the majority of the interventions seemed to be effective in older adults, similarly to what was seen in another study that looked at different ages [56]. This could be partly due to their acceptance of commonly used technologies [57], and also because patients with greater difficulties in the use of ICT can provide a close relative as their contact through the healthcare system.
Overall, ICT tools can be an additional strategy that could be used in health promotion campaigns to improve vaccine uptake in older adults, delivering information directly to the individuals at a relatively low cost.
5. Limitations
This systematic review has some limitations. Firstly, the included studies are heterogeneous in terms of their study setting, study populations, and type of intervention applied (e.g., the presence or absence of an educational component). This limits the potential of quantitatively pooling estimates and prevents meta-analysis. Secondly, many interventions are multicomponent, also including communicative strategies that involved traditional means of communication on top of the ICT, making it difficult to estimate the true effect of the technological tool alone. Finally, in this systematic review, the vast majority of RCTs were assessed with a low risk of bias (overall low risk of bias for 12 out of 15 studies, some concern for one and a high risk of bias for another). However, among the interventions with a study design other than RCTs (three non-RCTs and the four studies with before-and-after designs), the quality was lower on average, with four out of seven studies rated as being of low or moderate quality.
6. Conclusions
The ICT field has grown exponentially in recent years, becoming widely accessible to the general population. This review showed that ICT-based interventions could help to increase immunization coverage among older adults, with the majority of the included studies finding some level of effectiveness. However, further research is needed to assess how ICT can be optimally used to convey truly effective messages that improve public and individual health.
Author Contributions
Conceptualization: A.B. and V.B.; methodology: A.B. and G.G.; investigation: A.B., G.G. and M.T.; data curation: A.B. and G.G.; visualization: A.B., S.C. and V.B.; writing—original draft preparation: A.B., G.G. and M.T.; writing—editing supervision: A.B., S.C. and V.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research has received “Italian National Recovery and Resilience Plan—PNRR” (project PE0000015 “Age-It”—Spoke 4-task 2.4 Comprehensive public health protection for an aging population. D30_PNRR_PE8_S4_2) funds to cover publication costs. Funded by the European Union—NextGenerationEU.
Institutional Review Board Statement
The study adheres to the Declaration of Helsinki and Resolution No. 9/2016 of the Italian Personal Data Protection Authority, with the latter also confirming the permissibility of processing personal data for medical, biomedical, and epidemiological research, as well as the permissibility of using data concerning the status of people’s health in aggregate form in scientific studies.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Appendix A.1. Search Strategy: Keywords and Limits
| Axis 1 Keywords |
| influenza vaccin*; influenza immuni*; herpes zoster vaccin*; herpes zoster immuni*; shingles vaccin*; shingles immuni*; covid* vaccin*; covid* immuni*; pneumococc* vaccin*; pneumococc* immuni* |
| Axis 2 Keywords |
| text messag*; cell phone messag*; mobile phone messag*; cell phone; telephone; SMS messag*; MMS messag*; information technology; email*; application*; phone call*; reminder systems; social network*; social media; communications media; reminder*; recall* |
| Axis 3 Keywords |
| aged; elderly; older adult*; senior |
| Axis 4 Keywords |
| vaccination; vaccin* uptake; vaccin* coverage; vaccin* rate*; immunisation coverage; immunisation rate; vaccination hesitancy; vaccination refusal |
| Limits |
| The search strategy was limited to papers published between 1 January 2000, and 10 November 2022, human study populations and English language |
Appendix A.2. Search Strings Definition, Pubmed Database
((((text messag*[Title/Abstract]) OR (“Text Messaging”[Mesh]) OR (“Communications Media”[Mesh]) OR (cell phone messag*[Title/Abstract]) OR (“Cell Phone”[Mesh]) OR (mobile phone messag*[Title/Abstract]) OR (SMS messag*[Title/Abstract]) OR (“Reminder Systems”[Mesh]) OR (“Telephone”[Mesh]) OR (MMS messag*[Title/Abstract]) OR (information technology[Title/Abstract]) OR (email*[Title/Abstract]) OR (application*[Title/Abstract]) OR (phone call*[Title/Abstract]) OR (social network*[Title/Abstract]) OR (social media[Title/Abstract]) OR (reminder*[Title/Abstract]) OR (recall*[Title/Abstract])) AND ((elderly) OR (“Aged”[Mesh]) OR (older adult*) OR (senior)) AND ((influenza vaccin*[Title/Abstract]) OR (influenza immuni*[Title/Abstract]) OR (herpes zoster vaccin*[Title/Abstract]) OR (herpes zoster immuni*[Title/Abstract]) OR (shingles vaccin*[Title/Abstract]) OR (shingles immuni*[Title/Abstract]) OR (covid* vaccin*[Title/Abstract]) OR (covid* immuni*[Title/Abstract]) OR (pneumococc* vaccin*[Title/Abstract]) OR (pneumococc* immuni*[Title/Abstract])) AND ((“Vaccination”[Mesh]) OR (“Vaccination Coverage”[Mesh]) OR (“Vaccination Hesitancy”[Mesh]) OR (“Vaccination Refusal”[Mesh]) OR (vaccin* uptake[Title/Abstract]) OR (vaccin* coverage[Title/Abstract]) OR (vaccin* rate*[Title/Abstract]) OR (immunisation coverage[Title/Abstract]) OR (immunisation rate[Title/Abstract]))) AND ((“2000/01/01”[Date—Publication]: “2022/11/10”[Date—Publication]))) AND (“English”[Language])
Appendix A.3. Search Strings Definition, Scopus Dastabase
(TITLE-ABS (text AND messag*) OR TITLE-ABS (cell AND phone AND messag*) OR TITLE-ABS (mobile AND phone AND messag*) OR TITLE-ABS (sms AND messag*) OR TITLE-ABS (mms AND messag*) OR TITLE-ABS (information AND technology) OR TITLE-ABS (email*) OR TITLE-ABS (application*) OR TITLE-ABS (phone AND call*) OR TITLE-ABS (social AND network*) OR TITLE-ABS (social AND media) OR TITLE-ABS (reminder*) OR TITLE-ABS (recall*)) AND (ALL (elderly) OR ALL (older AND adult*) OR ALL (senior)) AND (TITLE-ABS (influenza AND vaccin*) OR TITLE-ABS (influenza AND immuni*) OR TITLE-ABS (herpes AND zoster AND vaccin*) OR TITLE-ABS (herpes AND zoster AND immuni*) OR TITLE-ABS (shingles AND vaccin*) OR TITLE-ABS (shingles AND immuni*) OR TITLE-ABS (covid* AND vaccin*) OR TITLE-ABS (covid* AND immuni*) OR TITLE-ABS (pneumococc* AND vaccin*) OR TITLE-ABS (pneumococc* AND immuni*)) AND (TITLE-ABS (vaccin* AND uptake) OR TITLE-ABS (vaccin* AND coverage) OR TITLE-ABS (vaccin* AND rate*) OR TITLE-ABS (immunisation AND coverage) OR TITLE-ABS (immunisation AND rate)) AND (LIMIT-TO (PUBYEAR, 2022) OR LIMIT-TO (PUBYEAR, 2021) OR LIMIT-TO (PUBYEAR, 2020) OR LIMIT-TO (PUBYEAR, 2019) OR LIMIT-TO (PUBYEAR, 2018) OR LIMIT-TO (PUBYEAR, 2017) OR LIMIT-TO (PUBYEAR, 2016) OR LIMIT-TO (PUBYEAR, 2015) OR LIMIT-TO (PUBYEAR, 2014) OR LIMIT-TO (PUBYEAR, 2013) OR LIMIT-TO (PUBYEAR, 2012) OR LIMIT-TO (PUBYEAR, 2011) OR LIMIT-TO (PUBYEAR, 2010) OR LIMIT-TO (PUBYEAR, 2009) OR LIMIT-TO (PUBYEAR, 2008) OR LIMIT-TO (PUBYEAR, 2007) OR LIMIT-TO (PUBYEAR, 2006) OR LIMIT-TO (PUBYEAR, 2005) OR LIMIT-TO (PUBYEAR, 2004) OR LIMIT-TO (PUBYEAR, 2003) OR LIMIT-TO (PUBYEAR, 2002) OR LIMIT-TO (PUBYEAR, 2001) OR LIMIT-TO (PUBYEAR, 2000)) AND (LIMIT-TO (DOCTYPE, “ar”)) AND (LIMIT-TO (LANGUAGE, “English”)) AND (EXCLUDE (SUBJAREA, “VETE”))
Appendix B
Table A1.
Quality assessment of the included studies. Cochrane Risk of Bias 2.0 (RoB 2) Tool for Randomized Controlled Trials.
Table A2.
Quality assessment of the included studies. Risk of Bias in Non-randomized Studies—of Interventions (ROBINS-I) for Non-Randomized Trials.
Table A3.
Quality assessment of the included studies. National Institutes of Health (NIH) Quality Assessment Tool for before–after (Pre–Post) Study with no Control Group.
References
- Global Vaccine Action Plan. Available online: https://www.who.int/teams/immunization-vaccines-and-biologicals/strategies/global-vaccine-action-plan (accessed on 24 February 2023).
- Adult Immunization Schedule—Healthcare Providers|CDC. 2023. Available online: https://www.cdc.gov/vaccines/schedules/hcp/imz/adult.html (accessed on 24 February 2023).
- Vaccination Coverage among Adults in the United States, National Health Interview Survey, 2019–2020 | CDC. 2022. Available online: https://www.cdc.gov/vaccines/imz-managers/coverage/adultvaxview/pubs-resources/vaccination-coverage-adults-2019-2020.html (accessed on 1 March 2023).
- European Centre for Disease Prevention and Control. Seasonal Influenza Vaccination and Antiviral Use in EU/EEA Member States—Overview of Vaccine Recommendations for 2017–2018 and Vaccination Coverage Rates for 2015–2016 and 2016–2017 Influenza Seasons. Stockholm: ECDC. 2018. Available online: https://www.ecdc.europa.eu/sites/default/files/documents/seasonal-influenza-antiviral-use-2018.pdf (accessed on 10 July 2023).
- Swain, P. European Pneumococcal Vaccination: A Progress Report. Available online: https://ilcuk.org.uk/wp-content/uploads/2023/01/ILC-European-Pneumococcal-Vaccination.pdf (accessed on 10 July 2023).
- Ozawa, S.; Portnoy, A.; Getaneh, H.; Clark, S.; Knoll, M.; Bishai, D.; Yang, H.K.; Patwardhan, P.D. Modeling The Economic Burden of Adult Vaccine-Preventable Diseases in the United States. Health Aff. 2016, 35, 2124–2132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McLaughlin, J.M.; McGinnis, J.J.; Tan, L.; Mercatante, A.; Fortuna, J. Estimated Human and Economic Burden of Four Major Adult Vaccine-Preventable Diseases in the United States, 2013. J. Prim. Prev. 2015, 36, 259–273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- E Talbird, S.; La, E.M.; Carrico, J.; Poston, S.; Poirrier, J.-E.; DeMartino, J.K.; Hogea, C.S. Impact of population aging on the burden of vaccine-preventable diseases among older adults in the United States. Hum. Vaccines Immunother. 2020, 17, 332–343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- CDC. Centers for Disease Control and Prevention. Flu & People 65 Years and Older. 2022. Available online: https://www.cdc.gov/flu/highrisk/65over.htm (accessed on 1 March 2023).
- Review of the Scientific Literature on Drivers and Barriers of Seasonal Influenza Vaccination Coverage in the EU/EEA. 2013. Available online: https://www.ecdc.europa.eu/en/publications-data/review-scientific-literature-drivers-and-barriers-seasonal-influenza-vaccination (accessed on 24 February 2023).
- Schlipköter, U.; Flahault, A. Communicable Diseases: Achievements and Challenges for Public Health. Public Health Rev. 2010, 32, 90–119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scotland, P.H. Interventions to Engage People Aged 60 Years and over in Influenza, Shingles and Pneumococcal Immunisation Programmes. Available online: http://www.healthscotland.scot/publications/interventions-to-engage-people-aged-60-years-and-over-in-influenza-shingles-and-pneumococcal-immunisation-programmes (accessed on 24 February 2023).
- Stockwell, M.S.; Fiks, A.G. Utilizing health information technology to improve vaccine communication and coverage. Hum. Vaccines Immunother. 2013, 9, 1802–1811. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Fifty-Eighth World Health Assembly, Geneva, 16–25 May 2005: Resolutions and Decisions, Annex; World Health Organization: Geneva, Switzerland, 2005; p. 143. [Google Scholar]
- NW 1615 L. St, Washington S 800, Inquiries D 20036 U 419 4300|857 8562|F 419 4372|M. Mobile Fact Sheet. Pew Research Center: Internet, Science & Tech. Available online: https://www.pewresearch.org/internet/fact-sheet/mobile/ (accessed on 1 March 2023).
- Bhaskar, S.; Bradley, S.; Chattu, V.K.; Adisesh, A.; Nurtazina, A.; Kyrykbayeva, S.; Sakhamuri, S.; Yaya, S.; Sunil, T.; Thomas, P.; et al. Telemedicine Across the Globe-Position Paper from the COVID-19 Pandemic Health System Resilience PROGRAM (REPROGRAM) International Consortium (Part 1). Front. Public Health 2020, 8, 556720. [Google Scholar] [CrossRef] [Scilit]
- Ammenwerth, E.; Neyer, S.; Hörbst, A.; Mueller, G.; Siebert, U.; Schnell-Inderst, P. Adult patient access to electronic health records. Cochrane Database Syst. Rev. 2021, 2021, CD012707. [Google Scholar] [CrossRef] [Scilit]
- Regan, A.K.; Bloomfield, L.; Peters, I.; Effler, P.V. Randomized Controlled Trial of Text Message Reminders for Increasing Influenza Vaccination. Ann. Fam. Med. 2017, 15, 507–514. [Google Scholar] [CrossRef] [Scilit]
- Otsuka, S.H.; Tayal, N.H.; Porter, K.; Embi, P.J.; Beatty, S.J. Improving Herpes Zoster Vaccination Rates through Use of a Clinical Pharmacist and a Personal Health Record. Am. J. Med. 2013, 126, 832.e1–832.e6. [Google Scholar] [CrossRef] [Scilit]
- Stinchfield, P.K. Practice-Proven Interventions to Increase Vaccination Rates and Broaden the Immunization Season. Am. J. Med. 2008, 121, S11–S21. [Google Scholar] [CrossRef] [Scilit]
- Mohammed, H.; McMillan, M.; Andraweera, P.H.; Elliott, S.R.; Marshall, H.S. A rapid global review of strategies to improve influenza vaccination uptake in Australia. Hum. Vaccines Immunother. 2021, 17, 5487–5499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lau, D.; Hu, J.; Majumdar, S.R.; Storie, D.A.; Rees, S.E.; Johnson, J.A. Interventions to improve influenza and pneumococcal vaccination rates among community-dwelling adults: A systematic review and meta-analysis. Ann Fam Med. 2012, 10, 538–546. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- E Thomas, R.; Lorenzetti, D.L. Interventions to increase influenza vaccination rates of those 60 years and older in the community. Cochrane Database Syst. Rev. 2018, 5, CD005188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stone, E.G.; Morton, S.C.; Hulscher, M.E.; Maglione, M.A.; Roth, E.A.; Grimshaw, J.M.; Mittman, B.S.; Rubenstein, L.V.; Rubenstein, L.Z.; Shekelle, P.G. Interventions that increase use of adult immunization and cancer screening services: A meta-analysis. Ann Intern Med. 2002, 136, 641–651. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balzarini, F.; Frascella, B.; Oradini-Alacreu, A.; Gaetti, G.; Lopalco, P.L.; Edelstein, M.; Azzopardi-Muscat, N.; Signorelli, C.; Odone, A. Does the use of personal electronic health records increase vaccine uptake? A systematic review. Vaccine 2020, 38, 5966–5978. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Odone, A.; Ferrari, A.; Spagnoli, F.; Visciarelli, S.; Shefer, A.; Pasquarella, C.; Signorelli, C. Effectiveness of interventions that apply new media to improve vaccine uptake and vaccine coverage. Hum. Vaccines Immunother. 2014, 11, 72–82. [Google Scholar] [CrossRef] [Scilit]
- Liberati, A.; Altman, D.G.; Tetzlaff, J.; Mulrow, C.; Gøtzsche, P.C.; Ioannidis, J.P.A.; Clarke, M.; Devereaux, P.J.; Kleijnen, J.; Moher, D. The PRISMA statement for reporting systematic reviews and meta-analyses of studies that evaluate health care interventions: Explanation and elaboration. PLoS Med. 2009, 6, e1000100. [Google Scholar] [CrossRef] [Scilit]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit]
- Sterne, J.A.C.; Hernán, M.A.; Reeves, B.C.; Savović, J.; Berkman, N.D.; Viswanathan, M.; Henry, D.; Altman, D.G.; Ansari, M.T.; Boutron, I.; et al. ROBINS-I: A tool for assessing risk of bias in non-randomised studies of interventions. BMJ 2016, 355, i4919. [Google Scholar] [CrossRef] [Scilit]
- National Institutes of Health (NIH). Quality Assessment Tool for before–after (Pre–Post) Study with no Control Group. Available online: https://www.nhlbi.nih.gov/health-topics/study-quality-assessment-tools (accessed on 26 April 2023).
- Biyik, M.V.; Arslan, I.; Taci, D.Y. Study to increase the pneumococcal vaccination rates of individuals aged 65 years and older. Prim. Health Care Res. Dev. 2020, 21, e37. [Google Scholar] [CrossRef] [Scilit]
- Desir, M.; Cuadot, A.; Tang, F. Addressing Barriers to COVID-19 Vaccination among Older U.S. Veterans. J. Community Health 2022, 47, 616–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghadieh, A.S.; Hamadeh, G.N.; Mahmassani, D.M.; Lakkis, N.A. The effect of various types of patients’ reminders on the uptake of pneumococcal vaccine in adults: A randomized controlled trial. Vaccine 2015, 33, 5868–5872. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hull, S.; Hagdrup, N.; Hart, B.; Griffiths, C.; Hennessy, E. Boosting uptake of influenza immunisation: A randomised controlled trial of telephone appointing in general practice. Br. J. Gen. Pract. 2002, 52, 712–716. [Google Scholar]
- Humiston, S.G.; Bennett, N.M.; Long, C.; Eberly, S.; Arvelo, L.; Stankaitis, J.; Szilagyi, P.G. Increasing Inner-City Adult Influenza Vaccination Rates: A Randomized Controlled Trial. Public Health Rep. 2011, 126, 39–47. [Google Scholar] [CrossRef] [Scilit]
- Kellerman, R.D.; Allred, C.T.; Frisch, L.E. Enhancing influenza immunization. Postcard and telephone reminders and the challenge of immunization site shift. Arch Fam Med. 2000, 9, 368–372. [Google Scholar] [CrossRef] [Scilit]
- Klassing, H.M.; Ruisinger, J.F.; Prohaska, E.S.; Melton, B.L. Evaluation of Pharmacist-Initiated Interventions on Vaccination Rates in Patients with Asthma or COPD. J. Community Health 2017, 43, 297–303. [Google Scholar] [CrossRef] [Scilit]
- Krieger, J.W.; Castorina, J.S.; Walls, M.L.; Weaver, M.R.; Ciske, S. Increasing influenza and pneumococcal immunization rates: A randomized controlled study of a senior center–based intervention. Am. J. Prev. Med. 2000, 18, 123–131. [Google Scholar] [CrossRef] [Scilit]
- Minor, D.S.; Eubanks, J.T.; Butler, K.R.; Wofford, M.R.; Penman, A.D.; Replogle, W.H. Improving influenza vaccination rates by targeting individuals not seeking early seasonal vaccination. Am. J. Med. 2010, 123, 1031–1035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strain, W.D.; Mansi, J.; Boikos, C.; Boivin, M.; Fisher, W.A. Achieving Influenza Vaccine Uptake Target in Canada via a Pharmacy-Led Telephone Discussion during the 2019–2020 Season. Vaccines 2021, 9, 312. [Google Scholar] [CrossRef] [Scilit]
- Winston. Increasing Pneumococcal Vaccination in Managed Care through Telephone Outreach—PubMed. Available online: https://pubmed.ncbi.nlm.nih.gov/17927463/ (accessed on 22 March 2023).
- Esteban-Vasallo, M.D.; Domínguez-Berjón, M.F.; García-Riolobos, C.; Zoni, A.C.; Torres, J.A.; Sánchez-Perruca, L.; Astray-Mochales, J. Effect of mobile phone text messaging for improving the uptake of influenza vaccination in patients with rare diseases. Vaccine 2019, 37, 5257–5264. [Google Scholar] [CrossRef] [Scilit]
- Patel, M.S.; Milkman, K.L.; Gandhi, L.; Graci, H.N.; Gromet, D.; Ho, H.; Kay, J.S.; Lee, T.W.; Rothschild, J.; Akinola, M.; et al. A Randomized Trial of Behavioral Nudges Delivered Through Text Messages to Increase Influenza Vaccination Among Patients With an Upcoming Primary Care Visit. Am. J. Health Promot. 2022, 37, 324–332. [Google Scholar] [CrossRef] [Scilit]
- Tubiana, S.; Labarere, J.; Levraut, J.; Michelet, P.; de Vaux, F.J.; Doumenc, B.; Hausfater, P.; Choquet, C.; Plaisance, P.; Schmidt, J.; et al. Effectiveness of a Multifaceted Informational-Based and Text Message Reminders on Pneumococcal and Influenza Vaccinations in Hospital Emergency Departments: A Cluster-Randomized Controlled Trial. Vaccines 2021, 9, 962. [Google Scholar] [CrossRef] [Scilit]
- Szilagyi, P.G.; Albertin, C.; Casillas, A.; Valderrama, R.; Duru, O.K.; Ong, M.K.; Vangala, S.; Tseng, C.H.; Rand, C.M.; Humiston, S.G.; et al. Effect of Patient Portal Reminders Sent by a Health Care System on Influenza Vaccination Rates: A Randomized Clinical Trial. JAMA Intern Med. 2020, 180, 962–970. [Google Scholar] [CrossRef] [Scilit]
- Szilagyi, P.G.; Albertin, C.S.; Casillas, A.; Valderrama, R.; Duru, O.K.; Ong, M.K.; Vangala, S.; Tseng, C.-H.; Humiston, S.G.; Evans, S.; et al. Effect of Personalized Messages Sent by a Health System’s Patient Portal on Influenza Vaccination Rates: A Randomized Clinical Trial. J. Gen. Intern. Med. 2021, 37, 615–623. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bedwick, B.W.; Garofoli, G.K.; Elswick, B.M. Assessment of targeted automated messages on herpes zoster immunization numbers in an independent community pharmacy. J. Am. Pharm. Assoc. 2017, 57, S293–S297.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hurley, L.P.; Beaty, B.; Lockhart, S.; Gurfinkel, D.; Breslin, K.; Dickinson, M.; Whittington, M.D.; Roth, H.; Kempe, A. RCT of Centralized Vaccine Reminder/Recall for Adults. Am. J. Prev. Med. 2018, 55, 231–239. [Google Scholar] [CrossRef] [Scilit]
- Stolpe, S.; Choudhry, N.K. Effect of Automated Immunization Registry-Based Telephonic Interventions on Adult Vaccination Rates in Community Pharmacies: A Randomized Controlled Trial. J. Manag. Care Spéc. Pharm. 2019, 25, 989–994. [Google Scholar] [CrossRef] [Scilit]
- Rand, M.L. Nursing Interventions Increase Influenza Vaccination Quality Measures for Home Telehealth Patients. J. Nurs. Care Qual. 2022, 37, 47–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loubet, P.; Kernéis, S.; Groh, M.; Loulergue, P.; Blanche, P.; Verger, P.; Launay, O. Attitude, knowledge and factors associated with influenza and pneumococcal vaccine uptake in a large cohort of patients with secondary immune deficiency. Vaccine 2015, 33, 3703–3708. Available online: https://pubmed.ncbi.nlm.nih.gov/26073016/ (accessed on 10 July 2023).
- Milkman, K.L.; Patel, M.S.; Gandhi, L.; Graci, H.N.; Gromet, D.M.; Ho, H.; Kay, J.S.; Lee, T.W.; Akinola, M.; Beshears, J.; et al. A megastudy of text-based nudges encouraging patients to get vaccinated at an upcoming doctor’s appointment. Proc. Natl. Acad. Sci. USA 2021, 118, e2101165118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dubé, È.; Ward, J.K.; Verger, P.; MacDonald, N.E. Vaccine Hesitancy, Acceptance, and Anti-Vaccination: Trends and Future Prospects for Public Health. Annu. Rev. Public Health 2021, 42, 175–191. [Google Scholar] [CrossRef] [Scilit]
- Solís Arce, J.S.; Warren, S.S.; Meriggi, N.F.; Scacco, A.; McMurry, N.; Voors, M.; Syunyaev, G.; Malik, A.A.; Aboutajdine, S.; Adeojo, O.; et al. COVID-19 vaccine acceptance and hesitancy in low- and middle-income countries. Nat. Med. 2021, 27, 1385–1394. [Google Scholar] [CrossRef] [Scilit]
- Bach, A.; Goad, J. The role of community pharmacy-based vaccination in the USA: Current practice and future directions. Integr. Pharm. Res. Pract. 2015, 4, 67–77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bay, S.L.; Crawford, D.J. Using Technology to Affect Influenza Vaccine Coverage among Children with Chronic Respiratory Conditions. J. Pediatr. Health Care 2017, 31, 155–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peek, S.T.M.; Wouters, E.J.M.; van Hoof, J.; Luijkx, K.G.; Boeije, H.R.; Vrijhoef, H.J.M. Factors influencing acceptance of technology for aging in place: A systematic review. Int. J. Med. Inform. 2014, 83, 235–248. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).