


Abstract
Oxidative stress contributes to aging-related muscle decline, but antioxidant interventions may affect functional and structural outcomes differently. This systematic review synthesized clinical, animal, and cellular evidence across clinically defined sarcopenia and broader models of aging-related muscle decline. PubMed, Embase, Web of Science, and Cochrane Central Register of Controlled Trials (CENTRAL) were searched through 11 July 2026. Eligible studies tested antioxidant interventions in older adults or aging-related preclinical models and were appraised using the Cochrane Risk of Bias 2 (RoB 2) tool, a modified Systematic Review Centre for Laboratory animal Experimentation (SYRCLE) risk-of-bias tool, and a modified in vitro checklist. Forty-four publications were included: eight clinical trials, 26 animal datasets, and 18 cellular datasets, with eight publications contributing both animal and cellular evidence. Comparative clinical benefits were reported primarily for strength or power (7/8 studies), with less support for physical performance (2/6 studies assessing this domain) or body composition-related muscle quantity (2/8 studies). Selected preclinical studies likewise showed functional gains without parallel structural improvement, although effects varied by model and intervention. Preclinical findings implicated antioxidant defense, mitochondrial maintenance, inflammation, and proteostasis, but most pathway evidence was associative and direct experimental validation was limited. Clinical evidence was further constrained by small samples, short interventions, combined nutritional or exercise co-interventions, and heterogeneous outcomes. Current evidence does not support a consistent increase in muscle quantity with antioxidant interventions. The observed pattern appears context dependent and requires confirmation in adequately powered, phenotype-stratified trials assessing muscle strength, physical performance, muscle quantity, and mechanistic endpoints.
1. Introduction
Sarcopenia is an age-related skeletal muscle disorder defined by the concurrent presence of low muscle mass and low muscle strength, while physical performance represents an important related outcome rather than a required diagnostic component under the Asian Working Group for Sarcopenia (AWGS) 2025 consensus [1]. Its global prevalence is approximately 10% [2], although estimates vary by population and diagnostic criteria. The AWGS provides regionally relevant assessment guidance [1]. Sarcopenia is associated with functional decline, systemic metabolic disturbances, and an increased risk of adverse health outcomes, including disability and mortality [2,3,4].
The pathogenesis of sarcopenia involves a multifaceted interplay of neuromuscular dysfunction, protein metabolic imbalance, and chronic inflammation [5]. A key contributor to this process is mitochondrial dysfunction, which has been implicated in skeletal muscle aging and sarcopenia [6]. Because skeletal muscle relies heavily on oxidative metabolism, excessive reactive oxygen species (ROS) production and impaired redox homeostasis may contribute to age-related muscle dysfunction [7]. In aging skeletal muscle, impaired mitochondrial quality control, including defective mitophagy, contributes to the persistence of dysfunctional mitochondria and disrupted muscle homeostasis [8]. Cellular senescence is also increasingly recognized as an important contributor to skeletal muscle aging and sarcopenia, where it may impair regenerative signaling, tissue homeostasis, and inflammatory regulation [9]. Importantly, experimental evidence indicates that aging and oxidative stress can impair excitation-contraction coupling (ECC) through alterations in membrane excitability and sarcoplasmic-reticulum calcium handling [10]. More broadly, the relative contribution of neuromuscular denervation, mitochondrial dysfunction, chronic inflammaging, nutritional deficiency, and anabolic resistance varies among individuals, indicating that sarcopenia comprises clinically and biologically heterogeneous phenotypes rather than a single uniform disorder [5].
Current management relies primarily on exercise, with nutritional interventions used as important adjuncts [1,11]. Antioxidant strategies have also attracted interest as potential adjuncts in aging-related muscle decline, with observational, clinical, and preclinical studies suggesting the possible benefits of selected vitamins and polyphenols [12,13,14,15]. Because exercise-induced ROS also act as physiological signals that contribute to mitochondrial and other training adaptations, the effects of antioxidant interventions are likely to depend on dose, timing, baseline antioxidant capacity, and exercise context rather than on indiscriminate ROS suppression [16]. Clinical findings nevertheless remain inconsistent, and their relationship to model-specific preclinical mechanisms is unclear.
Previous narrative reviews have examined flavonoids [17], microalgae-derived molecules [18], green tea polyphenols [19], and curcumin [20]. A recent meta-analysis evaluated antioxidant interventions with or without exercise in clinical populations [21], but did not integrate clinical outcomes with model-specific preclinical mechanisms. Because muscle strength and physical performance represent related but distinct functional domains, we synthesized them separately and examined whether changes in either domain occurred without parallel changes in body composition-related muscle quantity. This relationship was treated as an exploratory pattern rather than a predefined effect of antioxidant intervention. Accordingly, this review integrated clinical, animal, and cellular evidence across clinically defined sarcopenia and broader aging-related muscle decline, while distinguishing preclinical model contexts and the level of mechanistic validation.
2. Materials and Methods
2.1. Search Strategy
PubMed, Embase, Web of Science, and the Cochrane Central Register of Controlled Trials (CENTRAL) were searched on 11 July 2026. The strategy combined Medical Subject Headings with free-text terms for sarcopenia, muscle wasting, muscle loss, antioxidants, vitamins C and E, polyphenols, and flavonoids. Boolean operators were used to combine concepts and maximize retrieval sensitivity (Supplementary Table S1). No initial date restriction was applied. Reference lists of included studies and related reviews were also searched manually. Reporting followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses guidelines (PRISMA) [22]. Backward citation searching identified no additional eligible reports. This review was not prospectively registered in International Prospective Register of Systematic Reviews (PROSPERO) or another public repository.
2.2. Eligibility Criteria
Clinical studies were eligible if they enrolled adults with study-defined sarcopenia or a clearly defined form of aging-related muscle decline, including frailty, low muscle strength, low muscle mass, or mobility limitation. Because diagnostic definitions and age thresholds varied across the clinical literature, eligibility was based on the presence of an aging-related muscle phenotype rather than a uniform chronological-age cutoff. For interpretation of the clinical evidence, studies using explicit sarcopenia-related diagnostic or muscle-mass criteria were distinguished from those enrolling older adults with broader age-associated muscle impairment.
Animal studies were eligible if they investigated skeletal muscle outcomes in models relevant to aging-related muscle decline. These models included natural aging models, accelerated-aging or deficiency models, chemically induced aging-like models, and experimentally induced muscle-atrophy or disuse models. Chemically induced aging-like models included D-galactose exposure, whereas experimentally induced atrophy or disuse models included dexamethasone administration and hindlimb unloading. These induced models were included to examine specific oxidative, catabolic, or disuse-related mechanisms but were not considered biologically equivalent to spontaneous age-related sarcopenia.
Cellular studies included skeletal muscle cells exposed to senescence-inducing, oxidative-stress, mitochondrial-dysfunction, or atrophy-inducing conditions. Cellular models were used primarily to examine mechanistic pathways relevant to aging-related muscle decline rather than as direct models of clinically defined sarcopenia. Non-muscle cell models were eligible only when reported within an otherwise eligible study containing a skeletal muscle model and were treated as ancillary evidence rather than independent cellular datasets.
Eligible outcomes included structural outcomes, muscle function, cellular outcomes, redox markers, mitochondrial outcomes, and relevant mechanistic pathways. In this review, structural outcomes were interpreted according to their original measurement methods. Human studies reporting lean mass, appendicular skeletal muscle mass (ASM), or skeletal muscle index (SMI) were considered measures of body composition-related muscle quantity, whereas animal studies reporting muscle weight or myofiber cross-sectional area (CSA) were interpreted as tissue-level structural outcomes. Functional outcomes were interpreted as comprising two related but distinct domains: muscle strength, reflecting force-generating capacity, and physical performance, reflecting mobility-related functional capacity. Reviews, editorials, study protocols without outcome data, conference abstracts without sufficient data, and studies lacking an eligible model, intervention, or outcome were excluded. Reports that could not be retrieved were recorded separately and were not included in full-text eligibility assessment. Studies published in English with full text available were included to ensure consistent assessment of study methodology and outcome reporting. However, this criterion may introduce language-related selection bias, which is acknowledged as a limitation of the review. Accordingly, the study used clinical studies to identify human outcome signals, naturally aged animal models to assess physiological plausibility, induced animal models to examine mechanism-specific proof of concept, and cellular models primarily for pathway interrogation.
2.3. Study Selection and Data Extraction
Two reviewers independently selected studies and extracted data. EndNote 2025 was used to remove duplicates, followed by title and abstract screening and full-text eligibility assessment. Disagreements were resolved through discussion or consultation with a third senior reviewer. A standardized form captured the author, year, design, model, intervention type, dose, duration, and principal qualitative findings. A publication was defined as a distinct report, whereas an animal or cellular dataset represented a distinct in vivo or in vitro experimental component. Publications containing both animal and cellular experiments contributed to both dataset counts but were counted once in the publication total. Non-muscle cell experiments were treated as ancillary evidence and were not counted as independent cellular datasets.
2.4. Quality Assessment
Two reviewers independently assessed clinical trials with the Cochrane Risk of Bias 2 tool (RoB 2) [23]. Domains covered randomization, intervention deviations, missing outcomes, outcome measurement, and selective reporting. Each domain was rated as low risk, some concerns, or high risk. Animal studies were evaluated with the modified Systematic Review Centre for Laboratory animal Experimentation (SYRCLE) risk-of-bias tool [24], which adapts the Cochrane framework for laboratory experiments. Eight domains addressed sequence generation, baseline characteristics, housing, blinding, outcome assessment, missing data, selective reporting, and other biases. Cellular studies were appraised with a modified Toxicological data Reliability Assessment Tool (ToxRTool) checklist [25] covering model characterization, intervention specification, outcome measurement, and reporting completeness. Cellular evidence was used primarily to examine mechanisms rather than support clinical conclusions.
2.5. Data Synthesis
Meta-analysis was considered after studies were grouped by intervention category, outcome domain, and evidence level. Quantitative pooling was not performed because even the most comparable clinical subsets remained small and differed in intervention composition, co-interventions, participant characteristics, diagnostic criteria, outcome definitions, and measurement scales. For example, strength and physical-performance outcomes were assessed using non-interchangeable measures, while interventions within the same antioxidant category differed in compound, dose, duration, and co-intervention. We therefore used a qualitative synthesis to compare the direction and consistency of effects and mechanistic convergence across evidence levels.
For study-level counting of clinical outcomes, a study was counted as showing benefit in an outcome domain if it reported a statistically significant between-group difference in change, a group-by-time interaction, or an adjusted post-intervention between-group effect. Within-group pre–post changes alone were not counted as evidence of an intervention effect. Each study was counted no more than once within each outcome domain, regardless of the number of individual measures reported.
Antioxidant interventions were classified a priori into five primary categories for analytical assignment based on their principal hypothesized mechanism of action and the primary rationale described by the original investigators: (i) vitamins and antioxidant micronutrients; (ii) dietary polyphenols and plant-derived extracts; (iii) mitochondria-targeted or mitochondria-modulating antioxidants; (iv) nuclear factor erythroid 2-related factor 2 (Nrf2)-pathway activators and redox-responsive phytochemicals; and (v) thiol-containing or glutathione-supporting strategies. Because many antioxidants exert pleiotropic effects, each intervention was assigned to one primary category to avoid double counting. Secondary mechanisms were recorded separately and considered during mechanistic interpretation. These categories were prespecified before data synthesis and were used as a pragmatic analytical framework rather than biologically exclusive classifications. The study-level primary assignments, bases for classification, and experimentally supported secondary mechanistic actions are provided in Supplementary Table S2.
Mechanistic findings were narratively synthesized according to the number of supporting studies, evidence source, direction of reported effects, and consistency across independent studies. Evidence patterns were considered more consistent when similar outcomes were observed across multiple studies using comparable interventions or models, whereas heterogeneous findings or findings restricted to a single model were interpreted more cautiously. Mechanistic evidence was further interpreted according to the level of experimental validation. Findings based only on intervention-associated changes in pathway-related markers were classified as associative evidence, whereas evidence supported by pathway inhibition, gene silencing, or other loss-of-function approaches was classified as experimentally validated evidence. Where classification was ambiguous, assignments were discussed among the review team and finalized by consensus according to the predefined classification criteria.
3. Results
3.1. Search Results
The searches identified 2111 records. After deduplication, 1320 unique records remained, of which 1177 were excluded during title and abstract screening. Of 143 reports sought for retrieval, 24 could not be retrieved; 119 reports were therefore assessed for full-text eligibility. Seventy-five were excluded after full-text assessment, leaving 44 publications for inclusion. These publications contributed eight clinical trials, 26 animal datasets, and 18 cellular datasets. Eight publications contained both animal and cellular experiments and were counted once in the publication total but in both corresponding dataset categories [26,27,28,29,30,31,32,33]. Figure 1 presents the selection process.
Figure 1.
PRISMA 2020 [22] study-selection flow diagram.
The search identified 2111 records, of which 44 publications were included after screening and full-text eligibility assessment. Eight publications contributed both animal and cellular evidence.
3.2. Characteristics of Included Studies
3.2.1. Characteristics of Clinical Studies
Eight clinical trials evaluated antioxidant interventions across a spectrum of sarcopenia-related and broader age-associated muscle conditions. Eight randomized controlled trials were included; seven were double-blind, whereas one was a small pilot randomized trial [34]. All used oral supplements, including vitamins, polyphenols, and multinutrient formulations. Three trials combined supplementation with exercise training [14,35,36], and one trial evaluated nutritional supplementation on top of electrical muscle stimulation applied across all study groups [37]. Interventions lasted from 4 weeks to 6 months (Table 1). Both sexes were represented, although women generally predominated. Most studies adjusted for sex without testing sex-by-treatment interactions. Only Alway et al. performed a sex-stratified analysis and found no significant difference between men and women [14]. Evidence for sex-specific responses therefore remains limited. Diagnostic criteria for sarcopenia varied across studies. Bo et al. used cutoffs consistent with AWGS 2014 [38], whereas Liu et al. applied AWGS 2019 [35]. The marine oligomeric polyphenol pilot study used sex-specific appendicular lean mass cutoffs from the Foundation for the National Institutes of Health (FNIH) Sarcopenia Project [34], while the high-flavonoid cocoa study used skeletal muscle index thresholds derived from the original European Working Group on Sarcopenia in Older People (EWGSOP) definition [39]. The remaining trials recruited older adults with low muscle mass, frailty, or mobility limitations without requiring a formal diagnosis of sarcopenia.
Table 1.
Basic Characteristics of the Included Clinical Studies.
3.2.2. Outcome Measures
Outcomes were grouped into four domains. Body composition outcomes included lean mass, appendicular skeletal muscle mass, skeletal muscle index, and body fat percentage. Lean mass, appendicular skeletal muscle mass, and skeletal muscle index were interpreted as body composition-related measures of muscle quantity, whereas body fat percentage was treated as a broader body-composition measure. These measures were not considered equivalent to tissue-level structural outcomes assessed in preclinical studies, such as muscle weight or myofiber cross-sectional area. Functional outcomes included muscle strength and physical performance measures. Muscle strength outcomes included grip strength and knee-extension force, whereas physical performance outcomes included gait speed, Timed Up and Go, and five-repetition sit-to-stand tests. Biochemical outcomes included interleukin-6 (IL-6), tumor necrosis factor-α (TNF-α), C-reactive protein, and malondialdehyde. Quality of life was assessed with instruments such as the 36-Item Short Form Health Survey (SF-36) and the EuroQol 5-Dimension (EQ-5D).
3.2.3. Risk-of-Bias Assessment of Clinical Studies
Supplementary Figure S1 presents the domain-level judgments for individual clinical trials, whereas Supplementary Figure S2 summarizes the domain-level risk distribution. Seven of the eight clinical trials had a low overall risk of bias. One pilot study [34] had high risk because of missing outcomes and concerns about outcome measurement. This pilot study was therefore interpreted cautiously because of its high risk of bias and small sample size.
3.2.4. Characteristics of Preclinical Studies
The preclinical evidence comprised 36 publications, representing 26 animal and 18 cellular datasets. Eight studies included both in vivo and in vitro components to support mechanistic interpretation [26,27,28,29,30,31,32,33].
Animal studies were heterogeneous in their relationship to physiological aging and were therefore interpreted according to model context. Natural aging models included conventionally aged C57BL/6 mice [27,28,41,42,43,44], Wistar rats [45,46,47], Sprague-Dawley rats [48,49,50,51], and Fischer 344 × Brown Norway F1 rats [52,53]. Some studies superimposed additional nutritional or metabolic challenges on aged animals, including antioxidant deficiency, high-sucrose feeding, or high-fat feeding [46,54,55]. Accelerated-aging or deficiency models included senescence-accelerated mouse prone 8 (SAMP8) mice [26], OXYS rats [56], and senescence marker protein-30 knockout (SMP30-KO) mice subjected to vitamin C deficiency [57]. Chemically induced aging-like models included D-galactose exposure [33,58], whereas experimentally induced muscle-atrophy or disuse models included dexamethasone administration [29,30,32] and hindlimb unloading [31]. These induced models reproduce selected oxidative, catabolic, or disuse-related features relevant to aging-related muscle decline but were not considered biologically equivalent to spontaneous age-related sarcopenia. Detailed species, age, and model characteristics are provided in Table 2.
Table 2.
Basic Characteristics of the Included Preclinical Animal Studies.
C2C12 myoblasts were the principal cellular model. Most studies differentiated myoblasts into myotubes before inducing pathological stress. Cellular models included oxidative-stress, senescence/aging-like, and atrophy-related paradigms. Hydrogen peroxide was used to induce oxidative stress [31,59,60,61,62], whereas dexamethasone was used to model muscle-cell atrophy [29,30,32]. D-galactose was used as an aging-like or senescence-inducing stimulus [27,28,33,63], while other stressors included 2,2′-azobis(2-amidinopropane) dihydrochloride (AAPH) [64] and 7β-hydroxycholesterol [65]. One study evaluated mitochondrial respiratory responses in both myoblasts and myotubes [60], whereas another induced replicative senescence by serial passage of primary human myoblasts [66]. These cellular models were used primarily to interrogate pathways relevant to muscle aging rather than as direct equivalents of clinical sarcopenia.
Across the preclinical studies, interventions ranged from single compounds to multicomponent formulations. In animal models, monotherapies primarily utilized natural polyphenols (e.g., resveratrol, apigenin, and catechin) or essential vitamins (C and E). Several studies explored synthetic compounds designed for mitochondrial targeting, such as SkQ1 and XJB-5-131. In contrast, several investigations evaluated antioxidant blends, combining vitamins (A, E, and D) with essential trace elements (selenium and zinc) [45,46,54]. Other complex interventions included the polyphenolic mixture Taurisolo® (MBMed Company, Turin, Italy) [48] and the cystine-based antioxidant (F1) [43]. Administration protocols were predominantly oral, delivered via fortified feed or gavage, with durations spanning from 4 weeks to long-term interventions of up to 10 months.
Cellular studies tested isolated compounds, including ginsenosides [59], puerarin [67], and riboflavin [63], as well as tocotrienol-rich [66] and polyphenol-rich fractions [64]. Treatments were generally applied in vitro for 24–72 h (Table 3).
Table 3.
Basic Characteristics of the Included Preclinical Cellular Studies.
3.2.5. Risk-of-Bias Assessment of Animal Studies
The 26 animal datasets were assessed with the modified SYRCLE risk-of-bias tool. Supplementary Figure S3 reports per-study judgments, and Supplementary Figure S4 presents overall and selected domain-level summaries.
Overall, 21 of 26 datasets (80.8%) had unclear risk of bias, and five (19.2%) raised some concerns. None had low or high overall risk. Selective reporting, incomplete outcomes, and other biases were generally rated low risk. Sequence generation was adequate in 14 datasets. Blinding, housing, baseline comparability, and random outcome assessment were commonly unclear. Animal evidence was therefore characterized by substantial reporting uncertainty, particularly for blinding, housing, baseline comparability, and random outcome assessment, and preclinical mechanistic conclusions should be interpreted cautiously.
3.2.6. Quality Assessment of Cellular Studies
The 18 cellular datasets were evaluated with a modified ToxRTool framework for in vitro antioxidant research. Supplementary Figure S5 presents the criterion-level summary, whereas Supplementary Figure S6 presents the detailed study-level judgments. The methodological quality assessment across clinical, animal, and cellular evidence tiers is summarized in Figure 2.
Figure 2.
Evidence landscape and methodological quality. (a) Overall risk of bias in clinical trials. (b) Overall risk of bias in animal studies. (c) Overall methodological quality of cellular studies. The three panels use different appraisal frameworks and are not directly comparable. Abbreviations: RCTs, randomized controlled trials; RoB 2, Cochrane Risk of Bias 2; SYRCLE, Systematic Review Centre for Laboratory animal Experimentation; ToxRTool, Toxicological data Reliability Assessment Tool; Y, yes; PY, partly yes; NT, not tested; N, no.
Of 180 assessed criteria, 143 (79.4%) were fully met, 18 (10.0%) were partly met, and 19 (10.6%) were unmet. The weighted attainment was 84.4%. The three panels represent different appraisal frameworks and should not be directly compared. The weighted attainment shown for cellular studies reflects checklist fulfillment within the modified in vitro assessment framework. Objectives, test systems, controls, outcomes, and statistical methods were usually well described. Sixteen datasets reported adequate replication. Reporting of substance identification and concentration justification showed greater variability across studies. No study reported blinded outcome assessment, which particularly affects semiquantitative analyses such as immunofluorescence. Cellular findings therefore support target engagement and proof of concept but remain hypothesis-generating for whole-organism physiology.
3.3. Results by Antioxidant Class
Results are presented according to the five prespecified primary categories defined in the Methods. These categories were used only for analytical assignment; secondary mechanisms were cross-referenced without double counting. Primary assignments are shown in Table 4, with the rationale for classification and supported secondary mechanisms provided in Supplementary Table S2.
Table 4.
Analytical Classification and Evidence Distribution of Included Antioxidant Interventions.
3.3.1. Vitamins and Antioxidant Micronutrients
Two clinical studies evaluated vitamin or antioxidant-micronutrient interventions, and both reported improvements in muscle strength and at least one body composition-related muscle quantity measure [35,38]. However, these benefits occurred in the context of resistance training or protein-based nutritional support, and neither study demonstrated a clear additional benefit in physical performance. In the trial of vitamins C/E combined with resistance training, handgrip strength and knee-extension strength increased by approximately 2.5 kg and 1.3 kg more, respectively, than with resistance training alone. Skeletal muscle index and arm lean mass also showed additional increases of 0.29 kg/m2 and 0.37 kg, respectively, whereas total lean mass, leg lean mass, and mobility-related outcomes such as the Timed Up and Go test did not show clear additional improvement [35]. A 6-month trial of whey protein combined with vitamins D/E showed a similar outcome pattern: relative skeletal muscle index increased by approximately 0.18 kg/m2 and handgrip strength by approximately 2.7 kg, whereas appendicular skeletal muscle mass and mobility-related outcomes did not improve consistently [38].
Animal evidence included a vitamin C deficiency model, natural aging models, and naturally aged animals exposed to additional nutritional or metabolic challenges. Among these, the vitamin C deficiency model provided the clearest structural and functional evidence. In SMP30-KO mice, vitamin C deficiency reduced gastrocnemius and soleus weights to 74–83% of control values, decreased grip strength by 62% at week 16, and reduced endurance by more than 50%; these changes were restored after vitamin C repletion [57]. By contrast, in non-deficient or standard aged models, antioxidant mixtures more often altered redox or protein-metabolic indices, with limited recovery of muscle mass. A diet containing rutin, vitamins A/E, zinc and selenium restored leucine-stimulated protein synthesis in aged rats, but did not increase the weights of major hindlimb muscles [45]. In a sucrose-feeding model, lean-mass loss increased from 5.4% to 8.1%; antioxidant supplementation increased plasma antioxidant capacity and muscle protein concentration, but did not prevent the loss of lean mass or muscle mass [46]. A tocotrienol-rich fraction administered at 60 mg/kg/day for 3 months increased antioxidant enzyme activity, reduced lipid peroxidation and inflammation, and improved histological features, without clear evidence of restored muscle mass [50].
Cellular evidence further supported the effects of this category on redox and mitochondrial endpoints. D-galactose treatment increased the proportion of senescence-associated β-galactosidase (SA-β-gal)-positive C2C12 cells from 8.7% to 76.3%, whereas riboflavin reduced this proportion to 29.4%. D-galactose reduced adenosine triphosphate (ATP) levels by approximately 25%, and riboflavin restored ATP levels, together with improvements in myotube width and redox-related markers [63].
Overall, the benefits in this category were most apparent when treatment corrected a deficiency or accompanied resistance training or protein-based nutritional support.
3.3.2. Dietary Polyphenols and Plant-Derived Extracts
Dietary polyphenols and plant-derived extracts represented the largest and most heterogeneous intervention category. Among the six clinical studies of polyphenol or plant-derived interventions, five reported a significant comparative benefit in at least one muscle strength or power measure [14,36,37,39,40], and two reported a benefit in at least one physical-performance measure [34,39]. None demonstrated a significant comparative increase in body composition-related muscle quantity. When used as an exercise adjunct, resveratrol increased knee-extension peak torque by approximately 8% and average power by approximately 14%, but did not further improve lean mass compared with exercise alone [14]. Green tea extract improved right handgrip strength and right leg flexor peak torque; arm muscle mass decreased by approximately 80 g over 12 weeks in the control group, whereas a comparable decline was not observed in the intervention group. However, no clear between-group differences were found in whole-body or regional muscle mass [40]. In the initial cocoa cohort, skeletal muscle index increased within the flavanol group by approximately 0.8 kg/m2, but a significant between-group difference was not demonstrated. The average Timed Up and Go test time also improved within the flavanol group by approximately 0.7 s. In the separate follow-up cohort, flavanol-rich cocoa increased 6-min walking distance by approximately 35 m and improved several other mobility-related measures relative to non-flavanol cocoa, whereas handgrip findings differed between the two cohorts [39]. Schisandra extract and combined nutritional formulas containing curcumin or rutin mainly improved knee-extension strength and gait speed, with limited effects on lean mass or appendicular skeletal muscle mass [36,37].
In animal studies, polyphenol effects depended strongly on the specific compound and model used. Apigenin was one of the few interventions that improved both structural and functional outcomes in a natural aging model. Treatment at 50 mg/kg/day from 16 to 25 months of age increased hindlimb muscle weight and myofiber cross-sectional area, improved grip strength and running distance, and reduced frailty index scores [41]. In contrast, dark chocolate flavanols and (–)-epicatechin improved forelimb grip strength and inverted-screen performance, but did not change gastrocnemius weight [55]. Resveratrol studies in animals also showed that functional changes did not necessarily parallel changes in muscle mass: long-term supplementation reduced oxidative stress but did not preserve the weights of major hindlimb muscles, while another 6-month study improved ex vivo fatigue resistance, but tibialis anterior fiber cross-sectional area decreased by 8.6%, and treadmill endurance did not improve [42,44]. In 23-month-old rats, 8 weeks of (+)-epicatechin increased skeletal-muscle nicotinamide adenine dinucleotide (NAD+) by approximately 80%, increased NAD+/reduced nicotinamide adenine dinucleotide (NADH) ratio by more than 100%, increased complex I activity by approximately 100%, increased citrate synthase activity by more than 200%, and increased ATP content by approximately 90% [51]. Taurisolo® improved motor performance and antioxidant capacity in aged animals, but muscle mass was not measured [48].
Structural protection was reported mainly in experimentally induced atrophy or aging-like models. Lotus leaf extract, ferulic acid, amentoflavone and ginsenoside Ro improved myotube diameter, myofiber cross-sectional area, muscle mass or motor performance in dexamethasone, D-galactose or related stress models, accompanied by changes in acyl-CoA oxidase 1 (ACOX1)/muscle RING finger 1 (MuRF1), myostatin (MSTN)-SMAD signaling or mitochondrial-inflammatory pathways [29,30,32,33]. Among these, ginsenoside Ro increased gastrocnemius fiber cross-sectional area in D-galactose-treated mice from 1209.34 ± 89.76 μm2 to 1686.56 ± 90.68 μm2, and restored running time, running distance, maximum speed and grip strength [33]. Nobiletin likewise improved hindlimb muscle mass, lean mass, myofiber size, and skeletal-muscle function in D-galactose-treated mice, accompanied by activation of protein kinase B (Akt)/mechanistic target of rapamycin (mTOR)-related protein-synthesis signaling and suppression of forkhead box O3a (FoxO3a)/muscle atrophy F-box (MAFbx)/MuRF1-related protein-degradation signaling [58]. Because this study used a chemically induced aging-like model, its findings were interpreted as protection against D-galactose-associated atrophy rather than evidence from natural aging. Cellular studies mainly provided evidence for stress resistance, myogenic differentiation and proteostasis, with ferulic acid, amentoflavone and puerarin affecting ROS, MuRF1, myotube formation or myogenic marker expression [29,32,67]. These findings reflect protection against experimentally induced catabolic or aging-like stress and were considered separately from evidence obtained in natural aging models.
Simultaneous structural and functional improvement was uncommon in natural aging models, whereas structural protection was reported more often in induced atrophy or aging-like models.
3.3.3. Mitochondria-Targeted or Mitochondria-Modulating Antioxidants
No eligible clinical trial evaluated a mitochondria-targeted or mitochondria-modulating antioxidant in older adults with sarcopenia; evidence for this category was entirely preclinical. Representative interventions included pyrroloquinoline quinone (PQQ), SkQ1 and XJB-5-131. secreted protein acidic and rich in cysteine (SPARC)-guided edaravone nanoparticles were also included in this category because they involved targeted antioxidant delivery and mitochondrial redox-related outcomes, although the delivery strategy itself was not strictly mitochondria-targeted. Outcomes in this category focused on mitochondrial structure, respiratory-chain function and single-fiber contractile performance.
PQQ had both animal and cellular evidence. In aged mice, PQQ increased fast-twitch and total fiber cross-sectional area in the soleus, but did not change fiber number. Regarding physical performance outcomes, PQQ mainly improved pole test performance, whereas hanging time did not show a clear benefit [27]. In C2C12 cells, 50–100 nM PQQ reduced the 2.6-fold D-galactose-induced increase in ROS to near-control levels, and increased the fusion index from approximately 10% to approximately 40% [27]. SkQ1 mainly improved mitochondrial ultrastructure, but did not report muscle weight, grip strength, endurance or contractile force [56]. XJB-5-131 provided clearer functional data. In aged rats treated with 3 mg/kg three times per week for 4 weeks, gastrocnemius single-fiber maximal unloaded shortening velocity increased by 35% and absolute power by 58%; however, gastrocnemius fiber cross-sectional area and most muscle weights did not increase [52]. SPARC-guided edaravone nanoparticles preserved tibialis anterior and gastrocnemius weights in a 14-day hindlimb-unloading model and improved treadmill running distance; free edaravone did not show the same effect [31]. Because this study used an acute disuse model in young mice, its findings were interpreted as evidence of protection against disuse-induced atrophy rather than as evidence from physiological aging.
Existing results point more toward improvements in mitochondrial integrity, respiratory-chain function, and single-fiber contractile performance than toward increases in muscle mass. The absence of clinical data therefore represents a clear translational gap for strategies designed to target mitochondrial dysfunction.
3.3.4. Nrf2 Pathway Activators and Redox-Responsive Phytochemicals
No eligible clinical intervention was primarily assigned to the Nrf2-pathway category, and no included clinical trial directly measured Nrf2 target engagement in human skeletal muscle. Evidence for this category mainly came from C2C12 cells and a small number of animal studies. In H2O2-treated C2C12 myoblasts, platycodin D reduced ROS and apoptosis and protected mitochondrial membrane potential; Nrf2 small interfering RNA (siRNA) weakened its Nrf2/heme oxygenase-1 (HO-1) activation and cytoprotective effects [61]. Verbascoside and ginsenoside Rb1 were associated with improved mitochondrial respiration, cell survival, and bioenergetic indices, together with reduced oxidative stress [59,60]. Although apigenin and Taurisolo® were primarily classified as polyphenol-related interventions, they also provided cross-referenced evidence for endogenous antioxidant defense. Apigenin improved muscle structure, function and oxidative-damage markers in naturally aged mice, whereas Taurisolo® improved rotarod performance and antioxidant enzyme activity in aged rats [41,48].
Current evidence is therefore preclinical and primarily supports cytoprotective and endogenous antioxidant responses.
3.3.5. Thiol-Containing and Glutathione-Supporting Strategies
Evidence primarily assigned to this category came from the cystine-based formulation F1 [43]. Glutathione-related findings reported in vitamin or multinutrient studies [35,45,46] were considered as secondary cross-class mechanisms and were not reassigned to this primary category. Human evidence was indirect because glutathione-related changes were reported in multinutrient studies rather than in interventions assigned primarily to this category. In the vitamins C/E plus resistance-training trial, reduced glutathione (GSH) and the GSH/oxidized glutathione (GSSG) ratio increased while GSSG and malondialdehyde (MDA) decreased, but the contribution of glutathione-related mechanisms could not be separated from the effects of training and vitamin supplementation [35]. F1 was the main preclinical intervention in this category.
In animals, F1 showed structural protection and anti-apoptotic signaling, but functional outcomes are still lacking. As a glutathione precursor composed of L-cystine, glycine, selenomethionine and L-glutamine, F1 treatment for 6 months in aged mice increased gastrocnemius weight and myofiber cross-sectional area toward levels observed in young mice [43]. Aging reduced gastrocnemius weight by 17.3%; F1 increased relative gastrocnemius weight from 0.35 to 0.44 g per 100 g body weight, whereas the value in young mice was 0.62 g per 100 g body weight. F1 also restored the GSH/GSSG ratio, reduced 4-hydroxynonenal (4-HNE), increased mitochondrial superoxide dismutase 2 (SOD2), and reduced terminal deoxynucleotidyl transferase dUTP nick-end labeling (TUNEL)-positive muscle cells from approximately 11% to nearly 0%. This study did not report muscle strength or physical-performance outcomes. Selenium- and zinc-containing antioxidant mixtures restored leucine-stimulated protein synthesis or increased antioxidant capacity, but did not consistently prevent the loss of lean mass or muscle mass [45,46].
3.3.6. Cross-Class Outcome Patterns
Among clinical studies and natural-aging or deficiency models, structural benefits, including improvements in body composition-based muscle quantity measures or tissue-level structural outcomes (such as myofiber cross-sectional area), were most evident in four contexts: (i) vitamin deficiency correction, where the intervention addressed an overt nutritional deficit [57]; (ii) exercise or nutritional co-interventions, where the antioxidant served as an adjunct to resistance training or protein supplementation [35,38]; (iii) apigenin treatment in naturally aged mice, which was the sole polyphenol demonstrating simultaneous structural and functional improvement in a natural aging model [41]; and (iv) F1 supplementation, which partially restored gastrocnemius weight and increased myofiber cross-sectional area toward young-animal levels [43]. Structural preservation was reported particularly in chemically induced aging-like or experimentally induced atrophy/disuse models, including dexamethasone, D-galactose, and hindlimb unloading paradigms, whereas evidence from natural aging models was more limited. These findings from experimentally induced models were interpreted as evidence of protection against specific catabolic, oxidative, or disuse-related processes rather than direct evidence of efficacy against age-related sarcopenia. In contrast, mitochondrial and redox-related indices were often reported to change without measurable hypertrophy, particularly among mitochondria-targeted antioxidants and several polyphenol interventions. At the study level, seven of the eight clinical studies reported a significant comparative benefit in at least one muscle strength or muscle power measure [14,35,36,37,38,39,40]. Two studies reported a benefit in at least one physical-performance measure [34,39], corresponding to two of the six studies that assessed mobility- or balance-related performance. In contrast, only two of the eight studies demonstrated a significant comparative improvement in body composition-related muscle quantity [35,38]. Accordingly, six studies reported improvement in at least one selected functional outcome without a corresponding comparative increase in body composition-related muscle quantity [14,34,36,37,39,40]. These counts indicate study-level support for at least one outcome and should not be interpreted as consistent improvement across all measures within each study.
Selected functional and structural outcomes therefore did not always change in parallel. In the clinical studies, this pattern was driven mainly by strength or power, whereas evidence for physical performance was limited. Given the limited number and heterogeneity of clinical trials, this pattern should be considered hypothesis-generating rather than an established class-wide effect of antioxidant treatment.
3.3.7. Trials with Versus Without Exercise-Based Co-Interventions
Four of the eight clinical trials incorporated an exercise-based co-intervention: three combined supplementation with exercise training [14,35,36], whereas one applied electrical muscle stimulation to all study groups [37]. In these studies, the observed effects cannot be attributed solely to antioxidant supplementation. Vitamins C/E combined with resistance training produced additional gains of approximately 2.5 kg in handgrip strength and 1.3 kg in knee-extension strength relative to resistance training alone and also improved selected body composition indices, although total lean mass, leg lean mass, and physical-performance outcomes did not differ clearly between groups [35]. Resveratrol plus exercise increased knee-extension peak torque by approximately 8% and average power by approximately 14% without a parallel increase in lean mass [14]. Schisandra extract combined with low-intensity exercise improved knee-extension strength without a significant increase in muscle mass [36]. In the electrical-muscle-stimulation trial, whey protein, omega-3 fatty acids, and polyphenols increased knee-extension strength by approximately 13% relative to the carbohydrate control on top of electrical muscle stimulation (EMS), without a clear comparative improvement in muscle size [37]. Thus, three of these four studies reported strength or power-related benefits without a comparative increase in body composition-related muscle quantity [14,36,37], whereas the vitamins C/E trial reported improvements in both strength and selected body composition indices [35].
Four trials did not include an exercise-based co-intervention [34,38,39,40]. Whey protein combined with vitamins D/E increased relative skeletal muscle index and handgrip strength, although appendicular skeletal muscle mass and mobility outcomes did not improve consistently [38]. High-flavanol cocoa improved selected mobility outcomes, but between-group changes in muscle quantity and handgrip strength were inconsistent across cohorts [39]. Green tea extract improved selected strength outcomes without a clear between-group increase in whole-body or regional muscle mass [40]. The marine-polyphenol pilot study showed no clear comparative benefit for body composition, grip strength, Timed Up and Go, or chair-rise performance, although the one-leg stand test showed a marginal group-by-time interaction [34]. Separating trials according to exercise-based co-intervention clarifies the intervention context, but it does not isolate the independent contribution of antioxidant compounds from other nutritional components such as whey protein, vitamin D, or omega-3 fatty acids.
3.4. Molecular Mechanisms of Antioxidant Action
Mechanistic evidence was derived mainly from animal and cellular studies. Because the included clinical trials rarely assessed redox target engagement directly in skeletal muscle, these pathways should be interpreted as preclinical mechanisms associated with antioxidant interventions rather than confirmed mechanisms of clinical efficacy. We therefore distinguished experimentally validated pathways from associations based mainly on changes in molecular or functional markers. The multi-target mechanisms through which antioxidant interventions may influence these interconnected processes are summarized in Figure 3.
Figure 3.
Multi-target mechanisms of antioxidants against aging-related muscle decline. Abbreviations: ROS, reactive oxygen species; Nrf2, nuclear factor erythroid 2-related factor 2; HO-1, heme oxygenase-1; PGC-1α, peroxisome proliferator-activated receptor gamma coactivator 1-alpha; NRF1, nuclear respiratory factor 1; TFAM, mitochondrial transcription factor A; NAD+/NADH, nicotinamide adenine dinucleotide redox pair; ATP, adenosine triphosphate; AKT, protein kinase B; mTOR, mechanistic target of rapamycin; FoxO, forkhead box O; MuRF1, muscle RING-finger protein-1; LC3, microtubule-associated protein 1 light chain 3; PINK1, PTEN-induced kinase 1.
3.4.1. Mitochondrial Function and Bioenergetic Efficiency
Mitochondrial function represented one of the most frequently investigated mechanistic themes. XJB-5-131 increased single-fiber shortening velocity and power in aged rats without increasing muscle weight or myofiber cross-sectional area [52]. Mechanistically, this change was accompanied by increased activities of respiratory-chain complexes I, III and IV, whereas citrate synthase activity and electron transport chain (ETC) supercomplex abundance were unchanged. This pattern suggests improved mitochondrial functional efficiency rather than increased mitochondrial mass.
Other mitochondria-modulating interventions pointed in the same direction. SkQ1 mainly preserved mitochondrial ultrastructure in OXYS accelerated-aging rats, but did not assess muscle mass or functional outcomes [56]. In D-galactose-treated C2C12 cells, PQQ was associated with reduced ROS, increased mitochondrial number, an improved fusion index, and changes in peroxisome proliferator-activated receptor gamma coactivator 1-alpha (PGC-1α)/mitochondrial transcription factor A (TFAM)- and NAD+-related markers; however, evidence of skeletal-muscle target engagement in vivo was relatively weak [27]. Non-mitochondria-targeted antioxidants such as apigenin, riboflavin, verbascoside and (+)-epicatechin also repeatedly affected PGC-1α/nuclear respiratory factor 1 (NRF1)/TFAM, ATP, oxidative phosphorylation (OXPHOS) proteins, mitochondrial respiratory reserve or NAD+/sirtuin 1 (SIRT1)/PGC-1α-related metabolism [41,51,60,63]. Mitochondrial alterations therefore represented one of the most consistently reported mechanistic patterns across antioxidant categories; however, these findings were predominantly associative because none of the studies directly tested whether mitochondrial improvement was required for the observed muscle benefits.
3.4.2. Endogenous Antioxidant Defense and Cell Survival
Multiple studies showed that antioxidant interventions can enhance endogenous defense systems, although pathway validation varied. Platycodin D provided experimentally validated evidence for the involvement of the Nrf2/HO-1 pathway in a cellular model. H2O2 reduced C2C12 myoblast viability and markedly increased ROS, while platycodin D reduced ROS, protected mitochondrial membrane potential and decreased apoptosis. Nrf2 siRNA weakened its Nrf2/HO-1 activation and cytoprotective effects [61]. Verbascoside was also accompanied by Nrf2/HO-1 activation and improved mitochondrial respiratory reserve, but lacked Nrf2 loss-of-function validation, making it more appropriate to interpret as associative mechanistic evidence [60]. Thus, direct experimental validation of Nrf2/HO-1 dependence was provided by the platycodin D study, whereas the findings for verbascoside and other interventions were associative because they were based on pathway-related marker changes without loss-of-function validation.
In animal studies, Taurisolo®, apigenin, tocotrienol-rich fraction (TRF) and F1 all improved antioxidant enzyme activity, GSH/GSSG balance, lipid peroxidation or protein carbonylation [41,43,48,50]. Among these, F1 improved GSH/GSSG, 4-HNE, mitochondrial SOD2 and TUNEL-positive muscle cells [43]. Across these studies, antioxidant interventions were commonly accompanied by enhanced endogenous defense and improved cell survival, although most studies have not shown that these pathways are required for muscle protection.
3.4.3. Proteostasis, Anti-Atrophy Signaling and Myogenic Repair
Antioxidant interventions also affected protein synthesis, protein degradation and myogenic repair. A diet containing rutin, vitamins A/E, zinc and selenium restored leucine-stimulated protein synthesis in aged rats, but did not increase the weights of major hindlimb muscles [45]. Similarly, in a sucrose-feeding model, antioxidant supplementation increased muscle protein concentration and plasma antioxidant capacity, but did not prevent lean-mass or muscle-mass loss [46]. These findings indicate that improvements in protein-metabolic signaling do not necessarily translate into measurable hypertrophy.
Polyphenols and plant-derived compounds more frequently involved anti-atrophy pathways. Among these interventions, direct pathway validation was reported in two cellular studies. For oligonol combined with branched-chain amino acids, the L-type amino acid transporter 1 (LAT1) inhibitor JPH203 reversed the synergistic activation of mTOR/70-kDa ribosomal protein S6 kinase (p70S6K), while LAT1 silencing reduced branched-chain amino acids (BCAA)-related signaling [26]. In the puerarin study, inhibition of focal adhesion kinase (FAK) abolished puerarin-induced myoblast migration, whereas phosphoinositide 3-kinase (PI3K) inhibition suppressed PI3K/AKT activation and the associated enhancement of myoblast fusion and differentiation [67]. These findings support pathway dependence for specific cellular endpoints, but not for in vivo sarcopenia outcomes.
Dark chocolate flavanols and (-)-epicatechin improved functional performance and were accompanied by changes in the follistatin/myostatin ratio, myocyte enhancer factor 2A (MEF2A), forkhead box O1A (FOXO1A) and MuRF1, but did not increase gastrocnemius weight [55]. Lotus leaf extract, quercetin-3-O-glucoside (Q3G), ferulic acid and amentoflavone were associated with Akt/mTOR, Atrogin-1/MuRF1, ACOX1 and MSTN-SMAD pathways, respectively [29,30,32]. Nobiletin was also accompanied by increased Akt/mTOR-related signaling and reduced FoxO3a/MAFbx/MuRF1-related protein-degradation signaling in D-galactose-treated mice [58]. Because pathway inhibition or loss-of-function experiments were not performed, these findings were classified as associative rather than experimentally validated evidence. Except for the pathway-inhibition experiments involving oligonol and puerarin, most findings in this subsection were associative and were based on changes in Akt/mTOR, FoxO, MuRF1, ACOX1, MSTN-SMAD, or related markers.
3.4.4. Inflammation, Apoptosis and Mitochondrial Quality Control
Inflammation, apoptosis and mitochondrial quality control frequently changed together with redox or mitochondrial endpoints. PQQ, ginsenoside Ro and Taurisolo® reduced inflammation-related markers in animal models and were accompanied by improvements in antioxidant capacity or muscle performance [27,33,48]. In clinical studies, changes in inflammatory markers were inconsistent: vitamins C/E combined with resistance training reduced IL-6, whereas Schisandra extract improved knee-extension torque without clear changes in inflammatory or oxidative-stress markers [35,36]. Inflammation modulation may therefore contribute to some antioxidant responses, but it cannot explain all functional benefits.
Evidence related to apoptosis mainly came from animal and cellular studies. One cellular study provided direct experimental validation of redox-sensitive atrophic signaling. In calcitriol-treated C2C12 myotubes, N-acetylcysteine (NAC) and protein kinase C (PKC) inhibition attenuated ROS accumulation, mitochondrial membrane-potential loss, atrogene induction, and myotube atrophy, while c-Jun N-terminal kinase (JNK) inhibition prevented the reduction in myotube diameter [68]. These findings support a PKC–ROS–JNK-dependent mechanism for calcitriol-induced cellular atrophy, although they do not establish a protective antioxidant mechanism in aged muscle.
Platycodin D and trans-cinnamaldehyde both reduced H2O2-induced mitochondrial apoptosis-related changes [61,62]. F1 markedly reduced TUNEL-positive muscle cells in aged mice and was accompanied by changes in JNK, AMP-activated protein kinase (AMPK) and Akt-related signaling [43]. PQQ, apigenin and platycodin D also affected markers of mitochondrial quality control, including Parkin, BCL2-interacting protein 3 (BNIP3), p62 and microtubule-associated protein 1 light chain 3-II/I (LC3-II/I) [27,41,61]. These findings provided associative evidence for altered mitochondrial quality control. Because the treatment effects were not tested using autophagy- or mitophagy-specific inhibition, gene silencing, or rescue experiments, changes in Parkin, BNIP3, p62, or LC3-II/I should not be interpreted as evidence that these pathways were required for muscle protection.
3.4.5. Emerging Mechanisms Beyond Canonical ROS Scavenging
Several studies proposed mechanisms beyond direct ROS scavenging. Polygonatum polysaccharide was linked to mitochondria-associated membrane (MAM) and calcium-homeostasis regulation, involving changes in calcium-regulatory proteins such as inositol 1,4,5-trisphosphate receptor (IP3R) and voltage-dependent anion channel 1 (VDAC1) [28]. Ferulic acid was associated with reduced peroxisomal ACOX1 activity and downstream redox- and atrophy-related changes. Although pharmacological ACOX1 inhibition produced similar effects, the study did not demonstrate that ACOX1 was required for the response to ferulic acid [29]. In D-galactose-treated C2C12 cells, riboflavin restored ATP, myotube width and oscillation of core clock genes, suggesting a possible link between mitochondrial function and circadian rhythm [63]. PQQ and ginsenoside Ro also suggested that the gut barrier and gut-muscle axis may participate in muscle outcomes, but current evidence remains mainly model-based or associative [27,33].
These emerging mechanisms broaden the explanatory framework for antioxidant action, but the evidence remains limited. Based on the available data, mitochondrial function, endogenous antioxidant defense, proteostasis, and cell-survival pathways were the most frequently reported mechanistic themes, although most were supported by associative rather than experimentally validated evidence.
4. Discussion
This synthesis suggested a possible, although non-uniform, dissociation between selected functional and structural outcomes. Antioxidant interventions were associated with improvements in selected functional outcomes even when parallel gains in body composition-related muscle quantity or tissue-level structural measures were not observed. In clinical studies, this pattern was driven mainly by strength- or power-related outcomes: seven of eight studies reported a benefit in at least one such measure, whereas support was more limited for physical performance and body composition-related muscle quantity. Selected preclinical studies showed a similar but model-dependent pattern, with functional or contractile improvements not always accompanied by increases in muscle weight or myofiber size. This distinction is important because muscle strength and physical performance are related but non-interchangeable domains, reflecting force-generating capacity and integrated task performance, respectively.
Organizing the evidence by antioxidant category further showed that antioxidants should not be treated as a homogeneous intervention class. The categories differed in evidence source, outcome pattern, and mechanistic emphasis. In the two clinical studies of vitamins and antioxidant micronutrients, improvements in strength and selected muscle quantity measures occurred in the context of resistance training or protein-based nutritional support [35,38], whereas correction of vitamin C deficiency provided the clearest preclinical evidence in this category [57]. Among the six clinical studies of polyphenol or plant-derived interventions, five reported a benefit in at least one strength or power measure and two reported a benefit in physical performance, whereas none demonstrated a comparative increase in body composition-related muscle quantity [14,34,36,37,39,40]. Preclinical studies of polyphenols and mitochondria-modulating antioxidants broadened this evidence to mitochondrial, contractile, and tissue-level structural outcomes [41,51,52,55]. Nrf2- and glutathione-related strategies, by contrast, remain supported mainly by preclinical mechanistic evidence [43,60,61]. This classification therefore provides a practical framework for interpreting heterogeneous findings, but the categories should not be regarded as biologically exclusive because many antioxidants simultaneously influence redox, mitochondrial, inflammatory, and metabolic pathways.
Most studies did not directly measure muscle quality, such as intramuscular fat, muscle density, specific force, fiber quality or imaging-based parameters. The reported effects more commonly involved functional outcomes, including muscle strength and physical performance measures, mitochondrial endpoints, redox-related markers or histological features [14,35,39,41,50,51,52]. Future studies should combine muscle imaging, specific-force assessment, histology, mitochondrial evaluation, and separate measures of muscle strength and physical performance to clarify whether functional improvements occur independently of changes in muscle quantity or quality.
The observed differences between functional and structural outcomes should be interpreted cautiously. Functional outcomes may be more responsive than structural measures over short intervention periods, and several clinical trials included exercise or nutritional co-interventions that could preferentially affect muscle strength or physical performance. Although redox- or mitochondrial-related changes may precede detectable changes in muscle quantity, the available evidence does not establish such a temporal sequence. The apparent functional–structural divergence should therefore be considered hypothesis-generating rather than a demonstrated biological effect of antioxidant intervention. Redox biology should be interpreted in terms of homeostasis rather than simple ROS suppression. ROS are not exclusively damaging molecules but also serve as physiological signals involved in muscle contraction and exercise-induced adaptation [16]. Accordingly, the objective of antioxidant intervention should be restoration of an appropriate redox balance rather than maximal elimination of ROS. This framework may help explain why effects differ according to baseline nutritional or redox status, exercise exposure, dose, treatment duration, and disease context. It also highlights the possibility that high-dose antioxidant supplementation may attenuate beneficial exercise-induced redox signaling and selected skeletal-muscle adaptations [16,69]. Future studies should therefore define the appropriate compound, dose, timing, target population, and co-intervention context rather than assuming that stronger ROS suppression necessarily produces better outcomes.
This review has several limitations. The clinical evidence comprised only eight heterogeneous trials, several of which included exercise or multinutrient co-interventions and follow-up periods of no more than 6 months. These factors limited attribution of the observed effects to antioxidant compounds and may have reduced the ability to detect changes in muscle quantity. Women predominated in several studies, but sex-by-treatment interactions were rarely examined. Meta-analysis was not appropriate because of the limited number of comparable studies and the substantial heterogeneity in interventions, populations, and outcome definitions. Preclinical studies used models with differing relationships to physiological aging; chemically induced aging-like and experimentally induced atrophy or disuse models are useful for interrogating selected mechanisms but do not fully recapitulate spontaneous age-related sarcopenia [70]. In addition, few studies evaluated redox target engagement in human skeletal muscle. The review was not prospectively registered, was restricted to English-language full-text publications, and excluded reports that could not be retrieved, which may have introduced selection bias and reduced the completeness of the evidence base.
Given the limited clinical evidence, frequent use of combined interventions, and lack of target-engagement data in human skeletal muscle, antioxidants cannot currently be recommended as routine standalone treatment for sarcopenia or broader aging-related muscle decline. A more appropriate interpretation is that specific antioxidant strategies may improve selected outcomes in particular nutritional, exercise, or disease contexts, rather than that antioxidants exert a uniform therapeutic effect across populations.
An additional source of clinical variability is the heterogeneity of sarcopenia itself. Individual patients may differ in the relative contribution of neuromuscular denervation, mitochondrial dysfunction, chronic inflammaging, nutritional deficiency, and anabolic resistance; consequently, a single broad-spectrum antioxidant strategy is unlikely to produce uniform benefit [5]. Future clinical trials should stratify participants using clinically and mechanistically relevant features and align antioxidant selection with the dominant phenotype. Such phenotype-guided treatment may provide a more realistic framework for translating targeted preclinical findings into personalized clinical management.
Future evidence syntheses should avoid indiscriminate pooling of mechanistically distinct antioxidant interventions. In parallel, future trials should be organized more explicitly according to antioxidant category and mechanistic hypothesis. Studies of vitamins should distinguish deficient from non-deficient participants and clarify the contribution of exercise or protein-based nutritional support [35,38,57]. Polyphenol studies should measure physical performance, muscle composition, mitochondrial function and proteostasis in parallel, in order to distinguish functional improvement, metabolic remodeling and measurable structural preservation [14,29,30,32,33,39,40,41,51,55]. More broadly, future mechanistic studies should distinguish pathway-marker changes from direct assessment of skeletal-muscle protein turnover, particularly when translating proteostasis findings between animal models and humans [71]. Mitochondria-targeted antioxidants need to be tested in human sarcopenia trials and should include outcomes such as fatigue resistance, specific force or mitochondrial function [27,52,56]. Nrf2-related compounds need to move from cellular causal validation to animal and human target-engagement studies [60,61]. Glutathione-supporting strategies should incorporate muscle strength, walking ability and long-term muscle-mass outcomes [35,43]. Only when intervention components are clearly defined, follow-up is sufficiently long, and mechanistic indicators are measured alongside clinical outcomes can the translational potential of antioxidant strategies be properly evaluated.
5. Conclusions
In summary, antioxidant interventions across clinically defined sarcopenia and broader models of aging-related muscle decline did not produce uniform structural or functional responses. Clinical evidence suggested that the apparent functional–structural divergence was driven mainly by selected improvements in muscle strength or power, with more limited support for physical performance and body composition-related muscle quantity. Given the small and heterogeneous clinical evidence base, this pattern remains hypothesis-generating and requires confirmation in adequately powered trials with longer follow-up and concurrent assessment of strength, physical performance, and muscle quantity. Future trials should therefore stratify participants by dominant sarcopenic phenotype and align antioxidant selection with the relevant neuromuscular, mitochondrial, inflammatory, or nutritional context. Preclinical studies provided additional structural and mechanistic insights; however, most pathways were supported by associative changes in molecular markers, with direct experimental validation limited to a small number of cellular studies. Findings from accelerated-aging or deficiency, chemically induced aging-like, experimentally induced atrophy or disuse, and cellular models should therefore be regarded primarily as mechanistic evidence and should not be extrapolated directly to clinical sarcopenia.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/antiox15091167/s1, Figure S1: Cochrane RoB 2 domain-level assessment for individual clinical trials (n = 8); Figure S2: Cochrane RoB 2 domain-level risk distribution (n = 8 RCTs); Figure S3: Modified SYRCLE risk-of-bias assessment for individual animal studies (n = 26); Figure S4: Modified SYRCLE risk-of-bias domain-level distribution (n = 26); Figure S5: Cellular study quality: criterion-level summary (n = 18); Figure S6: In vitro quality assessment: modified ToxRTool (n = 18); Table S1: Search strategy: detailed search strings for each database; Table S2: Primary Analytical Classification and Experimentally Supported Secondary Mechanistic Actions in the 36 Preclinical Publications Reporting Mechanistic Outcomes.
Author Contributions
X.L., C.C. conceptualized this manuscript. X.L. drafted the original manuscript. X.L. and K.Z. collected the data. X.L. prepared figures and tables. C.C., R.M.Y.W. and W.H.C. reviewed and edited the manuscript. C.C. revised and finalized the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by the Collaborative Research Fund (Ref: C4032-21GF), the Health and Medical Research Fund Research Fellowship Scheme (Ref: 08220137), the General Research Grant (Ref: 14114822), and the Area of Excellence (Ref: AoE/M-402/20) and IdeaBooster Fund (Ref: IDBF23MED10).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
All data analyzed in this systematic review were derived from the published studies cited in the article. Extracted study characteristics and outcome data are summarized in the main tables, and methodological appraisal results are provided in the Supplementary Materials.
Conflicts of Interest
The authors declare no competing interests.
References
- Chen, L.-K.; Hsiao, F.-Y.; Akishita, M.; Assantachai, P.; Lee, W.-J.; Lim, W.S.; Muangpaisan, W.; Kim, M.; Merchant, R.A.; Peng, L.-N.; et al. A focus shift from sarcopenia to muscle health in the Asian Working Group for Sarcopenia 2025 Consensus Update. Nat. Aging 2025, 5, 2164–2175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yuan, S.; Larsson, S.C. Epidemiology of sarcopenia: Prevalence, risk factors, and consequences. Metab. Clin. Exp. 2023, 144, 155533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, Y.; Jiang, Y.; Guo, Y.; Pan, W.; Tian, W.; Tang, L.; Feng, X. Long-term impact of sarcopenia on functional decline and mortality in community-dwelling older adults: A systematic review and meta-analysis. Front Nutr. 2025, 12, 1652386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arthur Vithran, D.T.; Hassan, M.H.Y.; Rahmati, M.; Boyer, L.; Wehliye, A.A.; Xiao, W.; Li, Y. Adipose dysfunction, lipid dysregulation, and adipokines in sarcopenia: A systematic review and meta-analysis with sex-specific analyses. Age Ageing 2026, 55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, X.; Chen, X.; Cui, J. Therapeutic advances in sarcopenia management: From traditional interventions to personalized medicine. Clin. Nutr. 2025, 51, 187–197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marzetti, E.; Calvani, R.; Coelho-Junior, H.J.; Picca, A. Mitochondrial pathways and sarcopenia in the geroscience era. J. Nutr. Health Aging 2024, 28, 100397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, H.; Brown, J.L.; Bhaskaran, S.; Van Remmen, H. Reactive oxygen species in the pathogenesis of sarcopenia. Free Radic. Biol. Med. 2025, 227, 446–458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marzetti, E.; Calvani, R.; Coelho-Junior, H.J.; Landi, F.; Picca, A. Defective mitochondrial quality control in the aging of skeletal muscle. Mech. Ageing Dev. 2025, 228, 112112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Wang, H. Cellular Senescence in Skeletal Muscle Aging. Endocrinol. Metab. 2026, 41, 191–202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, H.; Ahn, B.; Van Remmen, H. Impact of aging and oxidative stress on specific components of excitation contraction coupling in regulating force generation. Sci. Adv. 2022, 8, eadd7377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, H.; Kim, J.; Lee, C.; Kim, S. Nutrition and exercise for sarcopenia treatment. Osteoporos. Sarcopenia 2025, 11, 54–64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yao, Y.; Yao, J.; Tang, D.; Wang, H.; Zhang, H.; Qiu, J.; Shu, X. Dietary antioxidant capacity and sarcopenia: A study from US population. Nutrition 2025, 130, 112613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, L.; Ding, X.; Zhang, Y.; Li, T.; Xu, P.; Ma, Y.; Xing, H.; Niu, Q.; Keerman, M. Serum concentrations of different or multiple vitamins and Sarcopenia risk among US adults: Insights from NHANES. BMC Public Health 2024, 24, 3372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alway, S.E.; McCrory, J.L.; Kearcher, K.; Vickers, A.; Frear, B.; Gilleland, D.L.; Bonner, D.E.; Thomas, J.M.; Donley, D.A.; Lively, M.W.; et al. Resveratrol Enhances Exercise-Induced Cellular and Functional Adaptations of Skeletal Muscle in Older Men and Women. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2017, 72, 1595–1606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, D.-Y.; Chun, Y.-S.; Kim, J.-K.; Lee, J.-O.; Ku, S.-K.; Shim, S.-M. Curcumin Attenuates Sarcopenia in Chronic Forced Exercise Executed Aged Mice by Regulating Muscle Degradation and Protein Synthesis with Antioxidant and Anti-inflammatory Effects. J. Agric. Food Chem. 2021, 69, 6214–6228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gonzalez, D.E.; Dickerson, B.L.; Roberts, B.M.; Kurtz, J.A.; Waldman, H.S.; Gonzalez, A.M.; McAllister, M.J.; Heileson, J.L.; Bloomer, R.J.; Arent, S.M.; et al. International Society of Sports Nutrition position stand: Effects of dietary antioxidants on exercise and sports performance. J. Int. Soc. Sports Nutr. 2026, 23, 2629828. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoon, Y.E.; Ju, S.H.; Kim, Y.; Lee, S.-J. Natural Flavonoids for the Prevention of Sarcopenia: Therapeutic Potential and Mechanisms. Int. J. Mol. Sci. 2025, 26, 7458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vignaud, J.; Loiseau, C.; Hérault, J.; Mayer, C.; Côme, M.; Martin, I.; Ulmann, L. Microalgae Produce Antioxidant Molecules with Potential Preventive Effects on Mitochondrial Functions and Skeletal Muscular Oxidative Stress. Antioxidants 2023, 12, 1050. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.; Xu, H.; Wu, S.; Guo, Y.; Zhao, G.; Wang, D. Mechanisms Underlying the Effects of the Green Tea Polyphenol EGCG in Sarcopenia Prevention and Management. J. Agric. Food Chem. 2023, 71, 9609–9627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saud Gany, S.L.; Chin, K.-Y.; Tan, J.K.; Aminuddin, A.; Makpol, S. Curcumin as a Therapeutic Agent for Sarcopenia. Nutrients 2023, 15, 2526. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Y.; He, Z.; Long, C.; Li, Y.; Yuan, Y.; Huang, T. Systematic review and meta-analysis of antioxidants with or without exercise training improving muscle condition in older adults. Sci. Rep. 2025, 15, 34356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.-Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hooijmans, C.R.; Rovers, M.M.; de Vries, R.B.M.; Leenaars, M.; Ritskes-Hoitinga, M.; Langendam, M.W. SYRCLE’s risk of bias tool for animal studies. BMC Med. Res. Methodol. 2014, 14, 43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schneider, K.; Schwarz, M.; Burkholder, I.; Kopp-Schneider, A.; Edler, L.; Kinsner-Ovaskainen, A.; Hartung, T.; Hoffmann, S. “ToxRTool”, a new tool to assess the reliability of toxicological data. Toxicol. Lett. 2009, 189, 138–144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, Y.-C.; Chen, Y.-C.; Chan, Y.-C.; Liu, C.; Chang, S.-J. Oligonol®, an Oligomerized Polyphenol from Litchi chinensis, Enhances Branched-Chain Amino Acid Transportation and Catabolism to Alleviate Sarcopenia. Int. J. Mol. Sci. 2024, 25, 11549. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohamad Ishak, N.S.; Kikuchi, M.; Ikemoto, K. Dietary pyrroloquinoline quinone hinders aging progression in male mice and D-galactose-induced cells. Front. Aging 2024, 5, 1351860. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, W.; Shen, Z.; Dong, W.; Huang, G.; Yu, D.; Chen, W.; Yan, X.; Yu, Z. Polygonatum sibiricum polysaccharide ameliorates skeletal muscle aging via mitochondria-associated membrane-mediated calcium homeostasis regulation. Phytomed. Int. J. Phyther. Phytopharm. 2024, 129, 155567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Y.; Tan, Y.; Song, Z.; Chen, Y. Ferulic acid attenuates Sarcopenia progression by inhibiting peroxisomal ACOX1. Free Radic. Biol. Med. 2025, 240, 183–196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, S.H.; Oh, J.; Jo, M.; Kim, J.K.; Kim, D.S.; Kim, H.G.; Yoon, K.; Yang, Y.; Geum, J.-H.; Kim, J.-E.; et al. Water Extract of Lotus Leaf Alleviates Dexamethasone-Induced Muscle Atrophy via Regulating Protein Metabolism-Related Pathways in Mice. Molecules 2020, 25, 4592. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kanazawa, G.; Maeda, H.; Yasuda, K.; Noguchi, I.; Nishinoiri, A.; Taguchi, K.; Imoto, S.; Tsukigawa, K.; Yamasaki, K.; Sakuragi, M.; et al. Secreted protein acidic and rich in cysteine-guided biomimetic delivery of nano-antioxidants reverses muscle atrophy in a mouse model of sarcopenia. J. Control. Release Off. J. Control. Release Soc. 2026, 391, 114567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lim, J.H.; Ahmad, S.S.; Lee, E.J.; Choi, J.-M.; Choi, I. Therapeutic potential of Amentoflavone against myostatin for skeletal muscle atrophy treatment: An in silico, in vitro, and in vivo study. Phytomed. Int. J. Phyther. Phytopharm. 2026, 157, 158323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, L.; Ding, X.; Ni, Y.; Wang, J.; Zhao, Y.; Wang, W.; Wu, J.; Liu, H.; Zhang, Y. Ginsenoside Ro ameliorates d-galactose-induced sarcopenia by modulating oxidative stress, inflammation, and gut microbiota in mice. Phytomed. Int. J. Phyther. Phytopharm. 2026, 157, 158307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kwon, I.-S.; Park, D.-S.; Shin, H.-C.; Seok, M.-G.; Oh, J.-K. Effects of marine oligomeric polyphenols on body composition and physical ability of elderly individuals with sarcopenia: A pilot study. Phys. Act. Nutr. 2021, 25, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, X.; Chen, B.; Jin, Y.; Zhong, F.; Zhang, Y.; Li, Y.; Zhang, Y.; Cui, R.; Wu, B.; Li, C.; et al. Effects of vitamins C and E supplementation combined with 12-week resistance training in older women with sarcopenia: A randomized, double-blind, placebo-controlled trial. Medicine 2025, 104, e43976. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, Y.H.; Lee, S.Y.; Lee, C.-H.; Park, J.-H.; So, Y.S. Effect of Schisandra chinensis Baillon extracts and regular low-intensity exercise on muscle strength and mass in older adults: A randomized, double-blind, placebo-controlled trial. Am. J. Clin. Nutr. 2021, 113, 1440–1446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boutry-Regard, C.; Vinyes-Parés, G.; Breuillé, D.; Moritani, T. Supplementation with Whey Protein, Omega-3 Fatty Acids and Polyphenols Combined with Electrical Muscle Stimulation Increases Muscle Strength in Elderly Adults with Limited Mobility: A Randomized Controlled Trial. Nutrients 2020, 12, 1866. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bo, Y.; Liu, C.; Ji, Z.; Yang, R.; An, Q.; Zhang, X.; You, J.; Duan, D.; Sun, Y.; Zhu, Y.; et al. A high whey protein, vitamin D and E supplement preserves muscle mass, strength, and quality of life in sarcopenic older adults: A double-blind randomized controlled trial. Clin. Nutr. 2019, 38, 159–164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Munguia, L.; Rubio-Gayosso, I.; Ramirez-Sanchez, I.; Ortiz, A.; Hidalgo, I.; Gonzalez, C.; Meaney, E.; Villarreal, F.; Najera, N.; Ceballos, G. High Flavonoid Cocoa Supplement Ameliorates Plasma Oxidative Stress and Inflammation Levels While Improving Mobility and Quality of Life in Older Subjects: A Double-Blind Randomized Clinical Trial. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2019, 74, 1620–1627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seo, H.; Lee, S.-H.; Park, Y.; Lee, H.-S.; Hong, J.S.; Lim, C.Y.; Kim, D.H.; Park, S.-S.; Suh, H.J.; Hong, K.-B. (-)-Epicatechin-Enriched Extract from Camellia sinensis Improves Regulation of Muscle Mass and Function: Results from a Randomized Controlled Trial. Antioxidants 2021, 10, 1026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, D.; Yang, Y.; Zou, X.; Zhang, J.; Zheng, Z.; Wang, Z. Antioxidant Apigenin Relieves Age-Related Muscle Atrophy by Inhibiting Oxidative Stress and Hyperactive Mitophagy and Apoptosis in Skeletal Muscle of Mice. J. Gerontol. A Biol. Sci. Med. Sci. 2020, 75, 2081–2088, Correction to: J. Gerontol. A Biol. Sci. Med. Sci. 2022, 77, 1173. https://doi.org/10.1093/gerona/glac086. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jackson, J.R.; Ryan, M.J.; Alway, S.E. Long-term supplementation with resveratrol alleviates oxidative stress but does not attenuate sarcopenia in aged mice. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2011, 66, 751–764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinha-Hikim, I.; Sinha-Hikim, A.P.; Parveen, M.; Shen, R.; Goswami, R.; Tran, P.; Crum, A.; Norris, K.C. Long-term supplementation with a cystine-based antioxidant delays loss of muscle mass in aging. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2013, 68, 749–759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toniolo, L.; Fusco, P.; Formoso, L.; Mazzi, A.; Canato, M.; Reggiani, C.; Giacomello, E. Resveratrol treatment reduces the appearance of tubular aggregates and improves the resistance to fatigue in aging mice skeletal muscles. Exp. Gerontol. 2018, 111, 170–179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marzani, B.; Balage, M.; Vénien, A.; Astruc, T.; Papet, I.; Dardevet, D.; Mosoni, L. Antioxidant supplementation restores defective leucine stimulation of protein synthesis in skeletal muscle from old rats. J. Nutr. 2008, 138, 2205–2211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gatineau, E.; Savary-Auzeloux, I.; Migné, C.; Polakof, S.; Dardevet, D.; Mosoni, L. Chronic Intake of Sucrose Accelerates Sarcopenia in Older Male Rats through Alterations in Insulin Sensitivity and Muscle Protein Synthesis. J. Nutr. 2015, 145, 923–930. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mosoni, L.; Gatineau, E.; Gatellier, P.; Migné, C.; Savary-Auzeloux, I.; Rémond, D.; Rocher, E.; Dardevet, D. High whey protein intake delayed the loss of lean body mass in healthy old rats, whereas protein type and polyphenol/antioxidant supplementation had no effects. PLoS ONE 2014, 9, e109098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Annunziata, G.; Jimenez-García, M.; Tejada, S.; Moranta, D.; Arnone, A.; Ciampaglia, R.; Tenore, G.C.; Sureda, A.; Novellino, E.; Capó, X. Grape Polyphenols Ameliorate Muscle Decline Reducing Oxidative Stress and Oxidative Damage in Aged Rats. Nutrients 2020, 12, 1280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zainul Azlan, N.; Mohd Yusof, Y.A.; Makpol, S. Chlorella vulgaris Ameliorates Oxidative Stress and Improves the Muscle Regenerative Capacity of Young and Old Sprague-Dawley Rats. Nutrients 2020, 12, 3752. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saud Gany, S.L.; Mohd Sahardi, N.F.N.; Tan, J.K.; Makpol, S. Correlation between oxidative stress and inflammation with metabolomics profile in skeletal muscle of ageing animal model and its modulation by tocotrienol-rich fraction. Br. J. Biomed. Sci. 2026, 83, 16208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramirez-Sanchez, I.; Ordoñez-Razo, R.; Najera, V.; Ceballos, G.; Villarreal, F. Stimulatory Effects of (+)-Epicatechin on Mitochondrial Biogenesis and Function in Skeletal Muscle of Aged Rats: Underlying Mechanisms. J. Med. Food 2026, 29, 489–497. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Javadov, S.; Jang, S.; Rodriguez-Reyes, N.; Rodriguez-Zayas, A.E.; Soto Hernandez, J.; Krainz, T.; Wipf, P.; Frontera, W. Mitochondria-targeted antioxidant preserves contractile properties and mitochondrial function of skeletal muscle in aged rats. Oncotarget 2015, 6, 39469–39481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joseph, A.-M.; Malamo, A.G.; Silvestre, J.; Wawrzyniak, N.; Carey-Love, S.; Nguyen, L.M.-D.; Dutta, D.; Xu, J.; Leeuwenburgh, C.; Adhihetty, P.J. Short-term caloric restriction, resveratrol, or combined treatment regimens initiated in late-life alter mitochondrial protein expression profiles in a fiber-type specific manner in aged animals. Exp. Gerontol. 2013, 48, 858–868. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Dijk, M.; Dijk, F.J.; Bunschoten, A.; van Dartel, D.A.M.; van Norren, K.; Walrand, S.; Jourdan, M.; Verlaan, S.; Luiking, Y. Improved muscle function and quality after diet intervention with leucine-enriched whey and antioxidants in antioxidant deficient aged mice. Oncotarget 2016, 7, 17338–17355. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Munguia, L.; Ramirez-Sanchez, I.; Meaney, E.; Villarreal, F.; Ceballos, G.; Najera, N. Flavonoids from dark chocolate and (-)-epicatechin ameliorate high-fat diet-induced decreases in mobility and muscle damage in aging mice. Food Biosci. 2020, 37, 100710. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vays, V.B.; Eldarov, C.M.; Vangely, I.M.; Kolosova, N.G.; Bakeeva, L.E.; Skulachev, V.P. Antioxidant SkQ1 delays sarcopenia-associated damage of mitochondrial ultrastructure. Aging 2014, 6, 140–148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takisawa, S.; Funakoshi, T.; Yatsu, T.; Nagata, K.; Aigaki, T.; Machida, S.; Ishigami, A. Vitamin C deficiency causes muscle atrophy and a deterioration in physical performance. Sci. Rep. 2019, 9, 4702. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, H.-H.; Zhang, Y.; Qu, T.-Q.; Sang, X.-Q.; Li, Y.-X.; Ren, F.-Z.; Wen, P.-C.; Sun, Y.-N. Nobiletin Improves D-Galactose-Induced Aging Mice Skeletal Muscle Atrophy by Regulating Protein Homeostasis. Nutrients 2023, 15, 1801. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, W.; Chen, W.; Zou, H.; Shen, Z.; Yu, D.; Chen, W.; Jiang, H.; Yan, X.; Yu, Z. Ginsenoside Rb1 Prevents Oxidative Stress-Induced Apoptosis and Mitochondrial Dysfunction in Muscle Stem Cells via NF-κB Pathway. Oxidative Med. Cell. Longev. 2022, 2022, 9159101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sciandra, F.; Bottoni, P.; De Leo, M.; Braca, A.; Brancaccio, A.; Bozzi, M. Verbascoside Elicits Its Beneficial Effects by Enhancing Mitochondrial Spare Respiratory Capacity and the Nrf2/HO-1 Mediated Antioxidant System in a Murine Skeletal Muscle Cell Line. Int. J. Mol. Sci. 2023, 24, 15276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, Y.H. Activation of the Nrf2/HO-1 signaling pathway contributes to the protective effects of platycodin D against oxidative stress-induced DNA damage and apoptosis in C2C12 myoblasts. General. Physiol. Biophys. 2020, 39, 519–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, Y.H. Trans-cinnamaldehyde protects C2C12 myoblasts from DNA damage, mitochondrial dysfunction and apoptosis caused by oxidative stress through inhibiting ROS production. Genes Genom. 2021, 43, 303–312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.; Sim, Y.; Lee, M.; Choi, Y.; Lim, J.Y.; Lee, J.-H.; Kim, E. Riboflavin as a circadian modulator mitigates D-galactose-induced muscle senescence via oxidative stress and mitochondrial regulation in C2C12 cells. J. Funct. Foods 2025, 130, 106924. [Google Scholar] [CrossRef] [Scilit]
- Kaminski, J.; Haumont, M.; Prost-Camus, E.; Durand, P.; Prost, M.; Lizard, G.; Latruffe, N. Protection of C2C12 skeletal muscle cells toward oxidation by a polyphenol-rich plant extract. Redox Exp. Med. 2023, 2023, e232002. [Google Scholar] [CrossRef] [Scilit]
- Ghzaiel, I.; Zarrouk, A.; Essadek, S.; Martine, L.; Hammouda, S.; Yammine, A.; Ksila, M.; Nury, T.; Meddeb, W.; Tahri Joutey, M.; et al. Protective effects of milk thistle (Sylibum marianum) seed oil and α-tocopherol against 7β-hydroxycholesterol-induced peroxisomal alterations in murine C2C12 myoblasts: Nutritional insights associated with the concept of pexotherapy. Steroids 2022, 183, 109032. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khor, S.C.; Wan Ngah, W.Z.; Mohd Yusof, Y.A.; Abdul Karim, N.; Makpol, S. Tocotrienol-Rich Fraction Ameliorates Antioxidant Defense Mechanisms and Improves Replicative Senescence-Associated Oxidative Stress in Human Myoblasts. Oxidative Med. Cell. Longev. 2017, 2017, 3868305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fang, X.; Xu, H.; Fan, Z.; Yang, H.; Huang, Y.; Xu, L.; Rong, Y.; Ma, W.; Pei, L.; Liang, H. Puerarin Promotes the Migration and Differentiation of Myoblasts by Activating the FAK and PI3K/AKT Signaling Pathways. Biology 2025, 14, 102. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raiteri, T.; Zaggia, I.; Reano, S.; Scircoli, A.; Salvadori, L.; Prodam, F.; Filigheddu, N. The Atrophic Effect of 1,25(OH)2 Vitamin D3 (Calcitriol) on C2C12 Myotubes Depends on Oxidative Stress. Antioxidants 2021, 10, 1980. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wyckelsma, V.L.; Murgia, M.; Kamandulis, S.; Gastaldello, S.; Brazaitis, M.; Snieckus, A.; Eimantas, N.; Pääsuke, M.; Edman, S.; Apro, W.; et al. Antioxidant supplementation blunts the proteome response to 3 weeks of sprint interval training preferentially in human type 2 muscle fibres. J. Physiol. 2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alonso-Puyo, J.; Izagirre-Fernandez, O.; Crende, O.; Valdivia, A.; García-Gallastegui, P.; Sanz, B. Experimental models as a tool for research on sarcopenia: A narrative review. Ageing Res. Rev. 2024, 101, 102534. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lim, C.; McKendry, J.; Lees, M.; Atherton, P.J.; Burd, N.A.; Holwerda, A.M.; van Loon, L.J.C.; McGlory, C.; Mitchell, C.J.; Smith, K.; et al. Turning over new ideas in human skeletal muscle proteostasis: What do we know and where to from here? Exp. Physiol. 2025, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
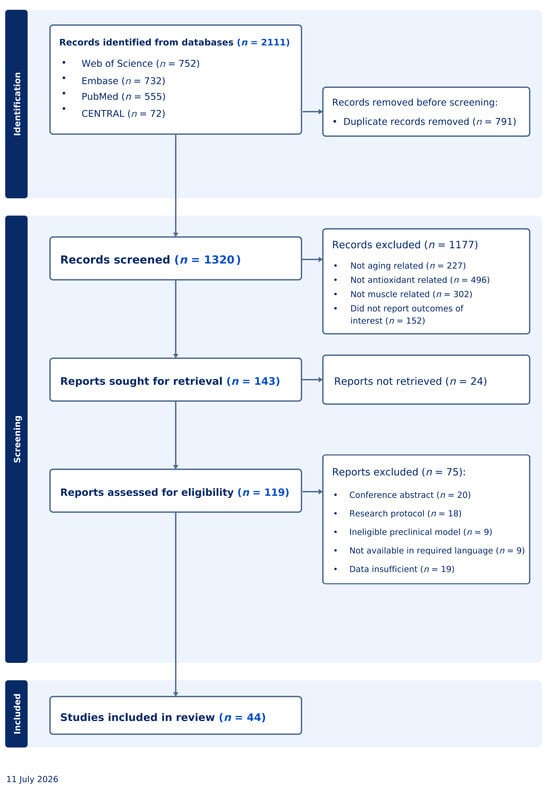
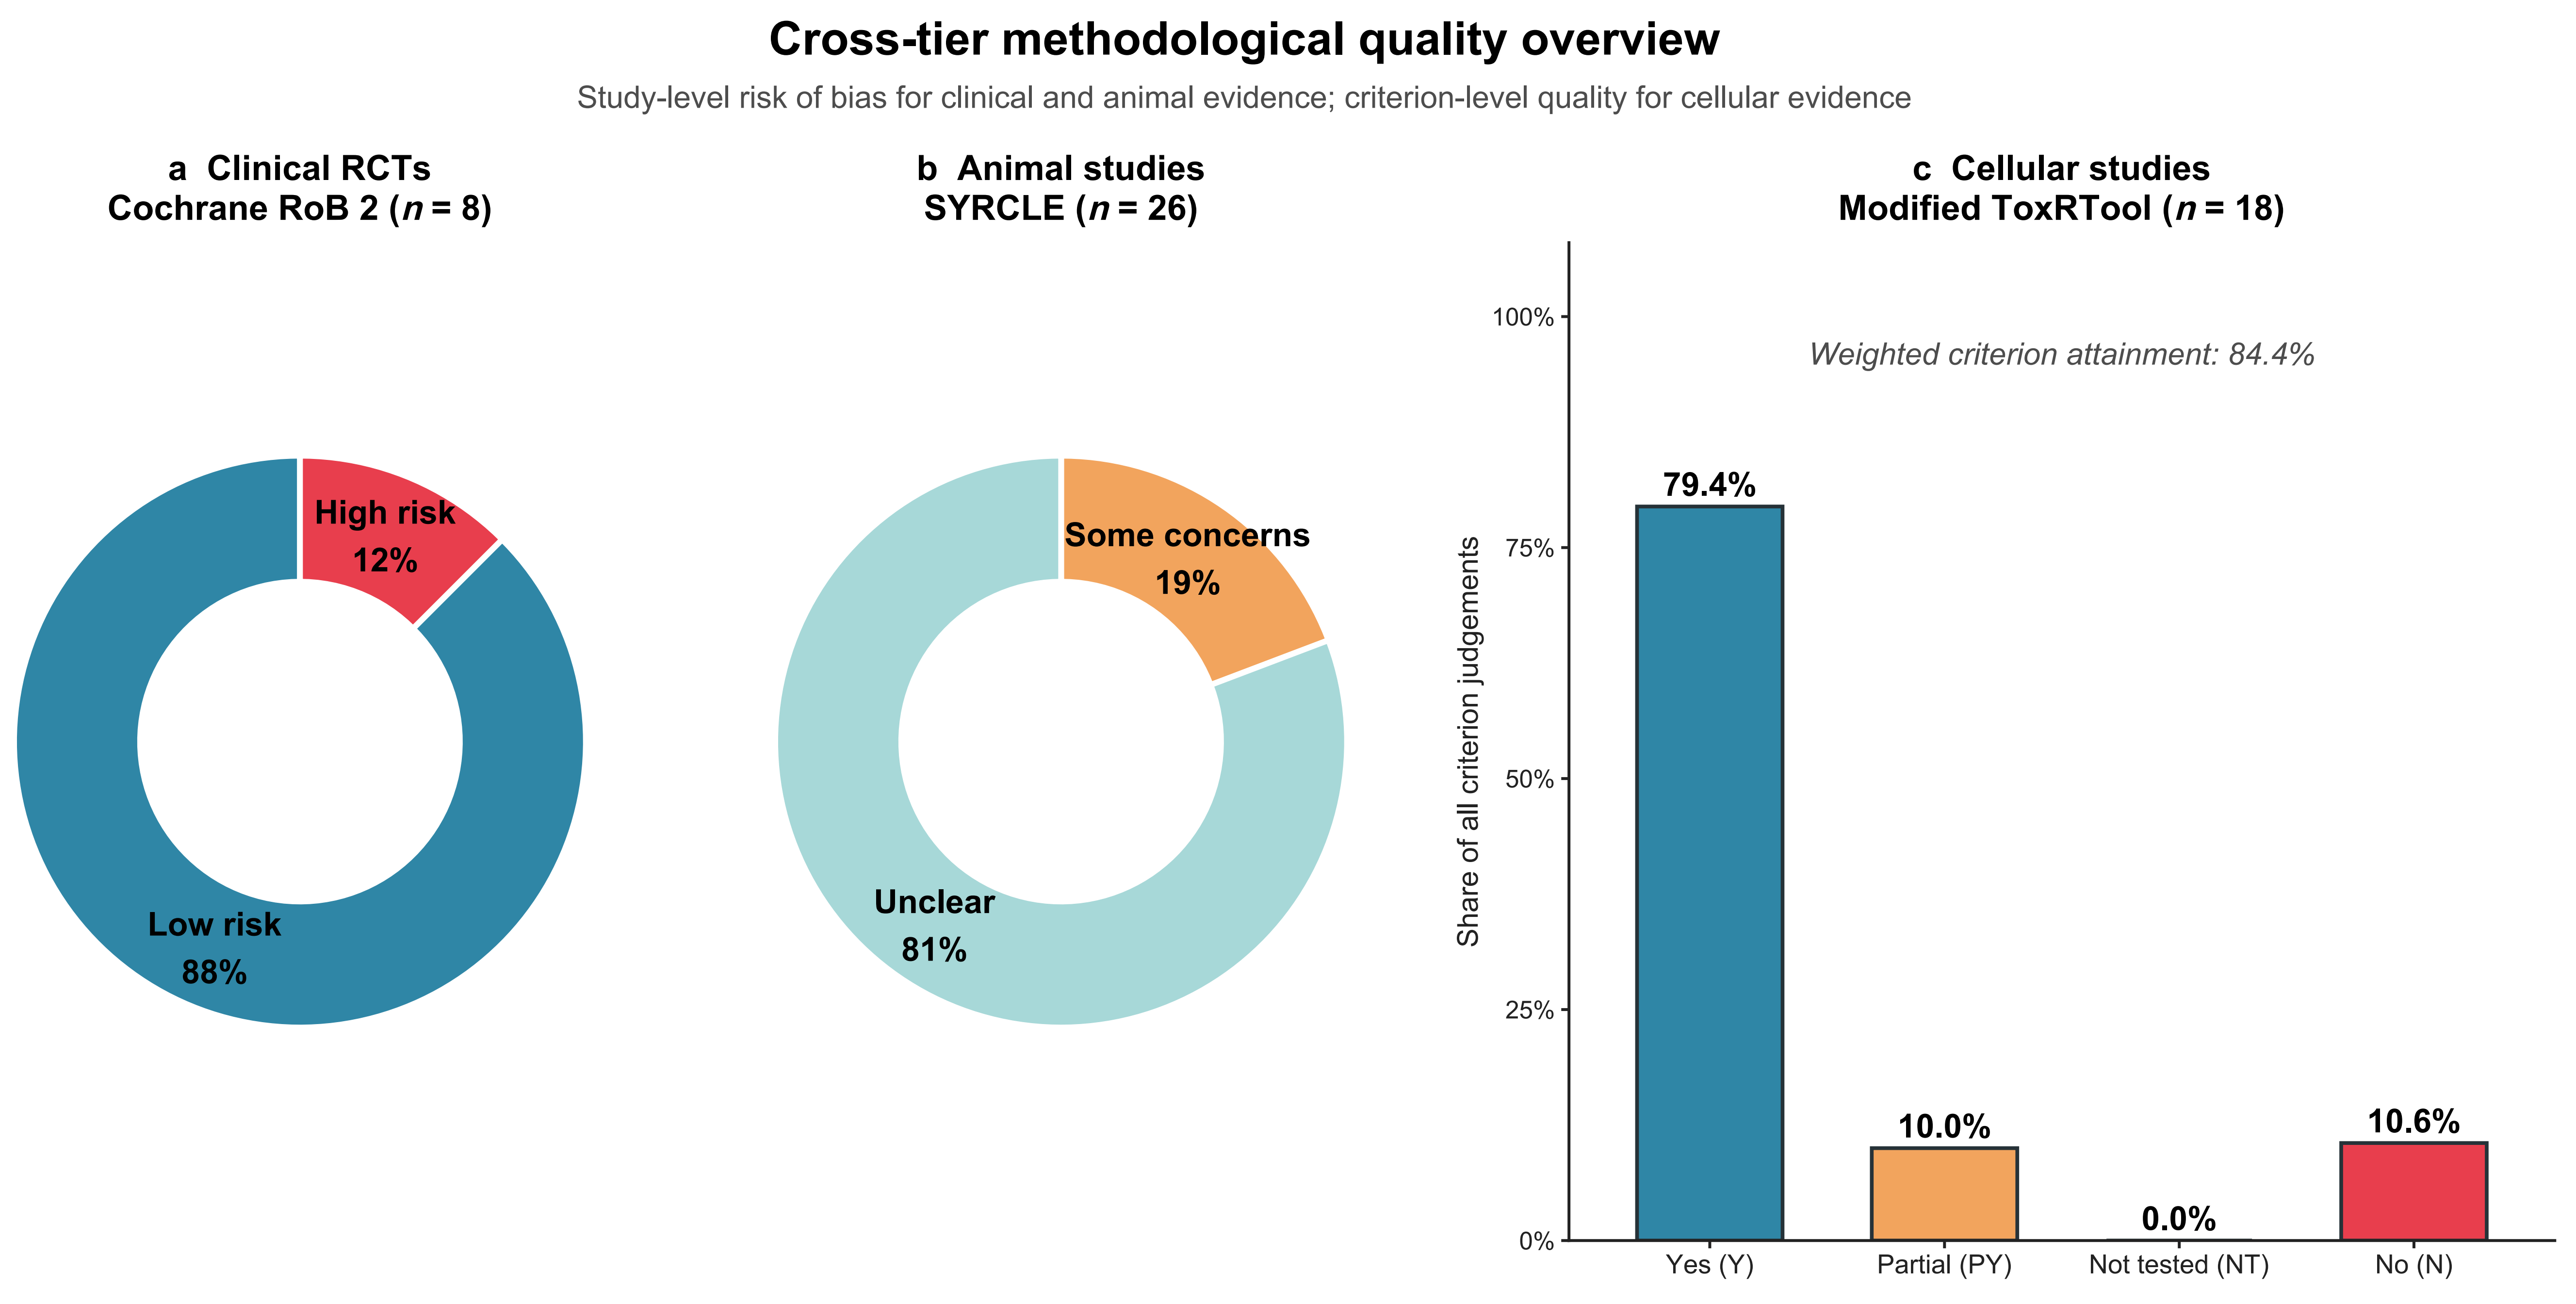
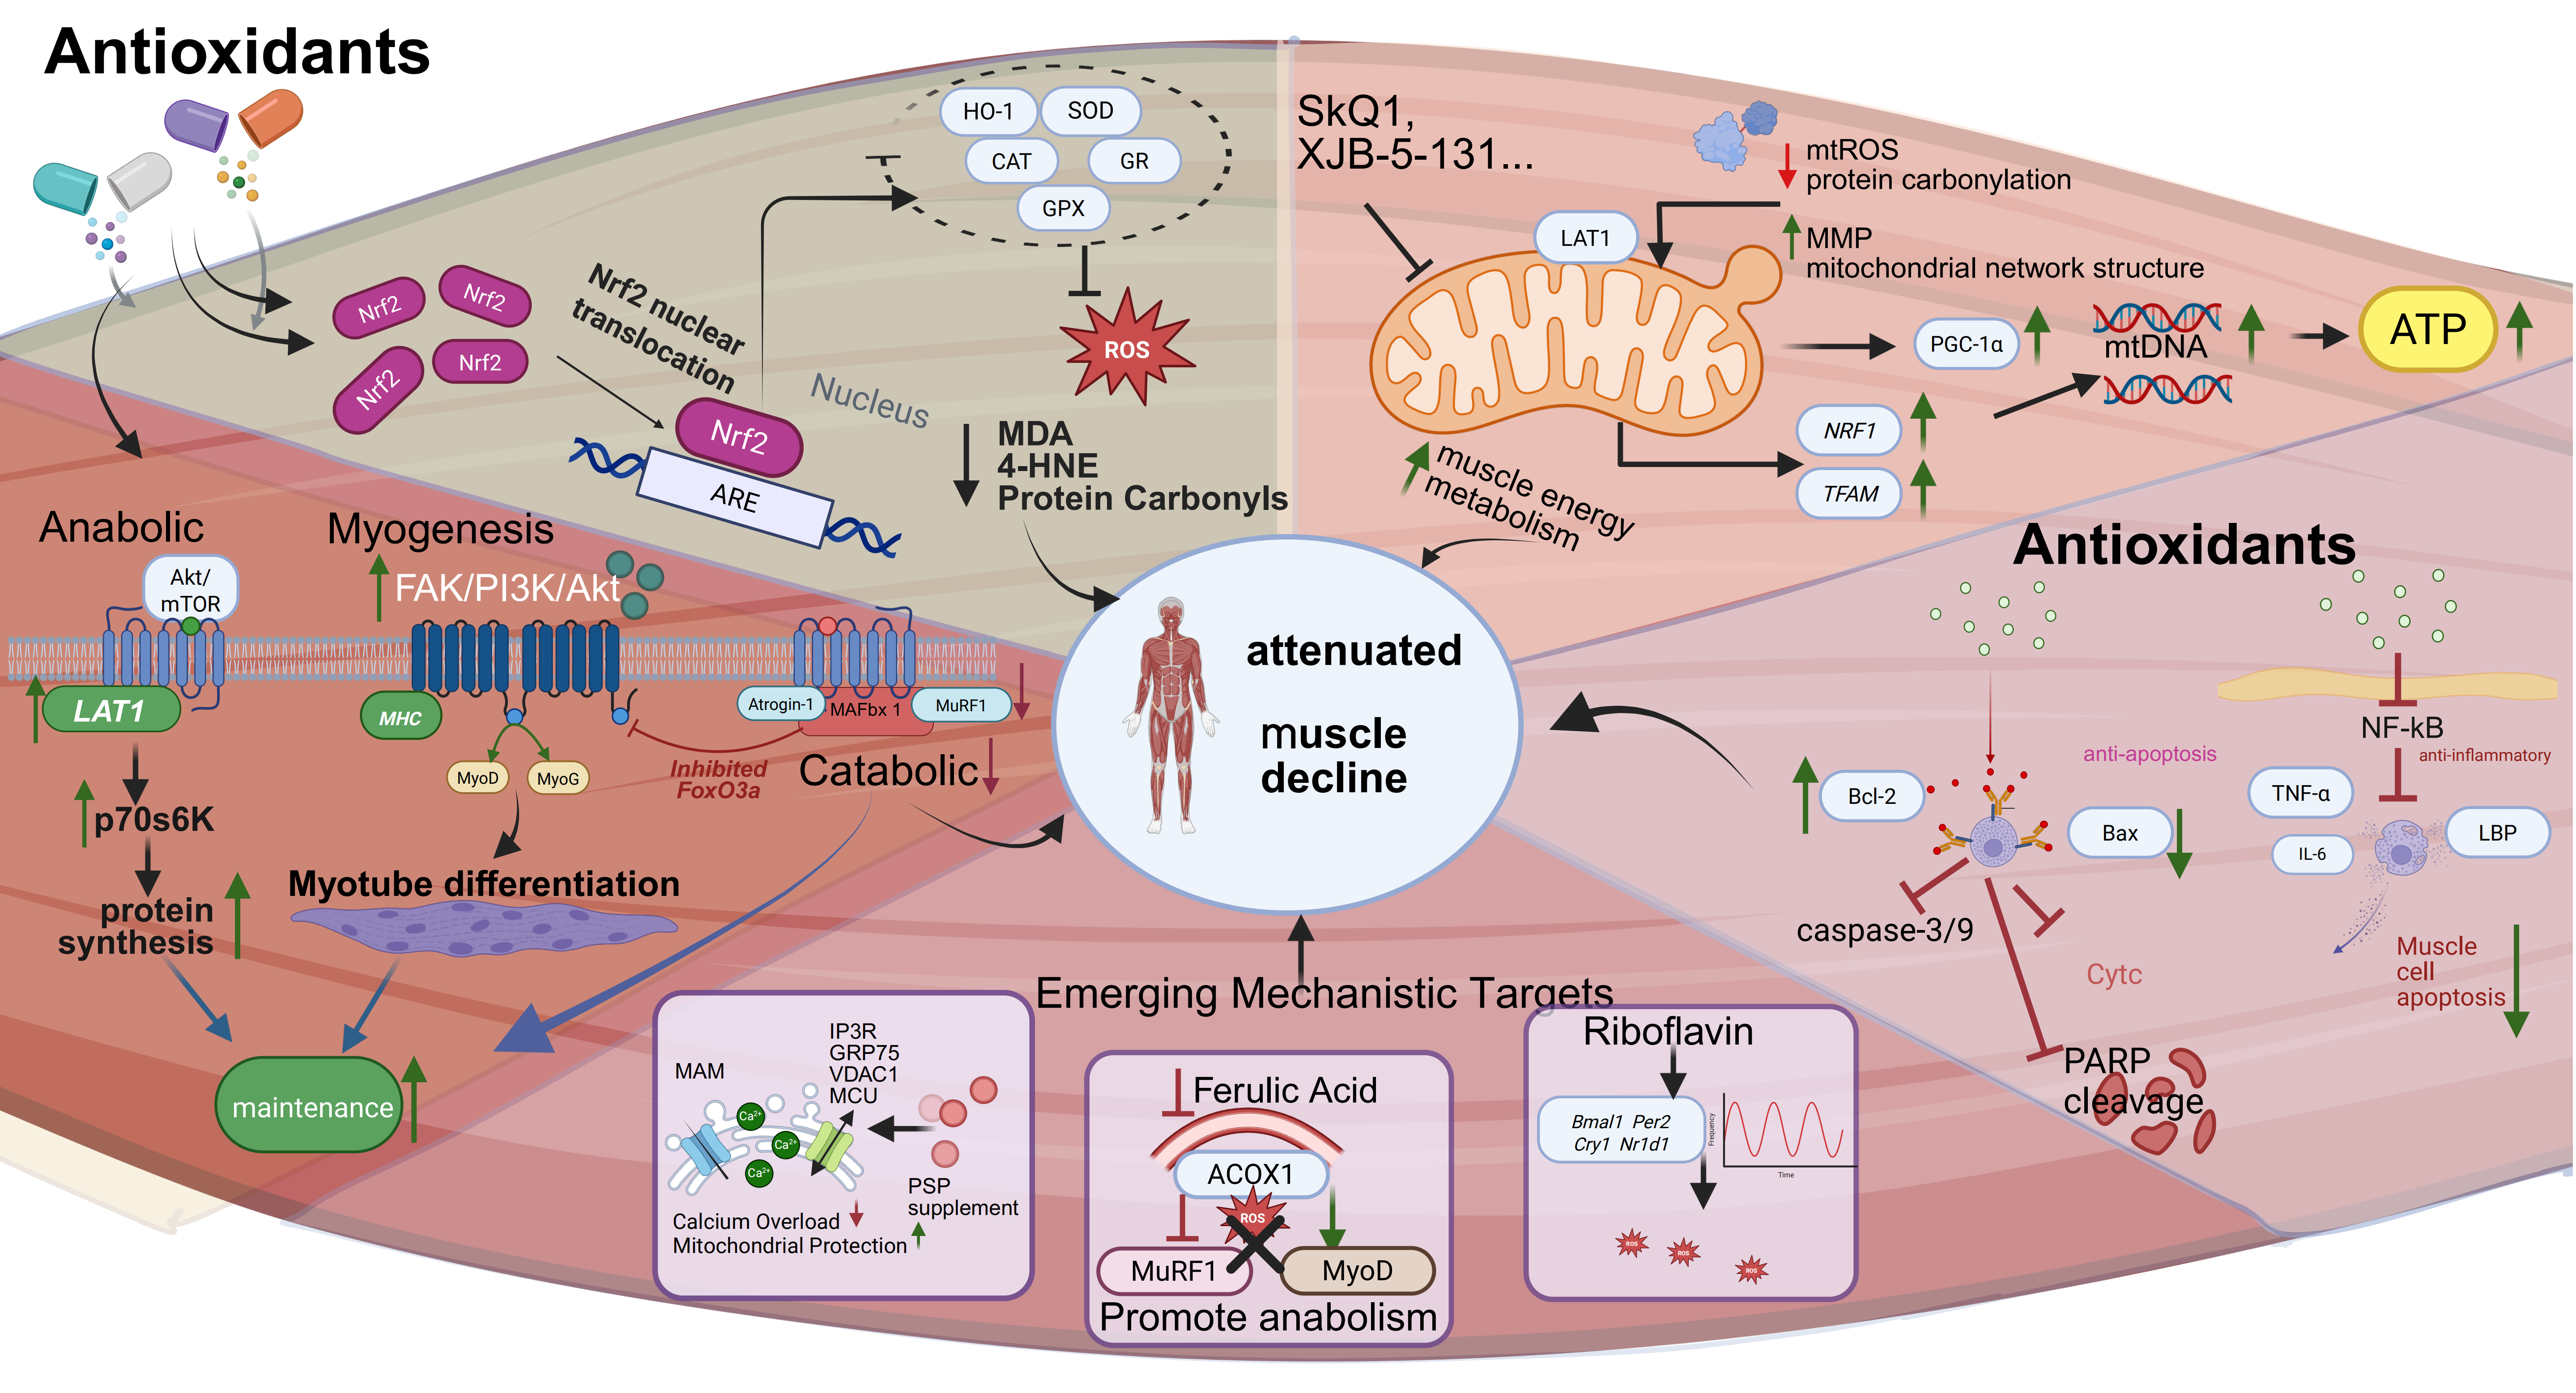

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.