


Featured Application
HeartHabit is a mobile health (mHealth) application developed to support user awareness, self-monitoring, and potential identification of symptoms of postpartum depression among Greek-speaking mothers during the first postpartum year. This study aims to inform the implementation of the app’s features, such as validated screening tools (e.g., EPDS), mood tracking, self-regulation support, and connection with health professionals.
Abstract
Postpartum depression (PPD) affects a substantial proportion of women globally and is often underdiagnosed due to barriers in screening, stigma, and limited access to care. This study presents the design and pilot evaluation of an mHealth application (“HeartHabit”) intended to support user awareness, self-monitoring, and potential identification of symptoms of PPD among Greek-speaking mothers. An alpha version of the application was evaluated through an online survey with 30 women within the first postpartum year, using a walkthrough video. The evaluation focused on perceived usability and acceptability rather than clinical outcomes or real-world use. Usability and app quality were assessed via the System Usability Scale (SUS) and a qualitative version of the user Mobile Application Rating Scale (uMARS), respectively, adopting a mixed-methods approach. Demographics, and mood and stress screening data were also captured. Quantitative data were analysed via descriptive statistics and qualitative responses via Framework Analysis. The results indicated high perceived usability (mean SUS = 83.7/100). Qualitative findings highlighted the importance of practical usability, self-regulation tools, personalisation, and connectivity with healthcare professionals. Privacy, data transparency, and user control over personal data were perceived as critical for trust. The application was perceived as a potentially useful adjunct to formal care or as at-home support when access to services is limited. Larger, controlled trials, clinical implementation protocols and clinician training are needed to promote the app’s safe integration into formal care. This mixed-methods evaluation, incorporating usability assessment and patient involvement, may offer a useful paradigm for early-stage digital mental health intervention development.
1. Introduction
Postpartum depression (PPD) is a common public health concern worldwide, with a global prevalence estimated at 15–20% [1,2,3]. Rates are often higher in developing countries [1,2,3]. In Europe, reported rates range from 10 to 15%; in Greece specifically, the figure reaches 13.2% [4,5]. PPD is classified as a Major Depressive Episode with onset within four weeks of delivery [6,7,8]. It does not constitute a stand-alone diagnosis in the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5), but it links to non-psychotic, depressive symptoms such as persistent low mood and functional impairment, distinguishing it from brief “baby blues” [6]. Other common symptoms may include sleep and appetite disturbance, fatigue, irritability or anxiety, feelings of worthlessness or guilt, poor concentration, and even suicidal thoughts [6].
Clinical evidence indicates that symptoms may appear anytime within the first year postpartum [4,7]. Risk factors span personal, medical and psychosocial levels. Demographics such as young maternal age, low socioeconomic status or education, multiple children, and being a single parent increase PPD odds [4]. Poor diet and lack of exercise, prior history of mood disorders, and pregnancy-related stress, such as complications, high-risk pregnancy or birth trauma, also correlate with PPD occurrence [5,9]. From a psychosocial perspective, low social support, marital conflict, financial strain, and stressful life events increase PPD risk, with domestic violence and intimate partner abuse dramatically elevating it [4,10]. This multi-faceted risk of PPD and likelihood of later onset may impede early detection.
Early identification and appropriate management of PPD are important for reducing adverse outcomes [4,11]. In contrast, untreated PPD is strongly associated with mothers’ poorer physical health, relationship difficulties, persistent depression, substance use, and suicide [10,12]. Infants of depressed mothers are also at higher risk of poor cognitive, emotional and social development, behavioural problems, and even medical disorders in adolescence [12]. The relevant literature indicates that 50% of PPD cases are undiagnosed, and of the clinically diagnosed cases, around 50% will remain undertreated [13,14]. A lack of structured screening methods, follow-up protocols and stigma contribute to this [11,13]. It is, thus, critical that flexible screening and follow-up methods are offered throughout the first year of delivery. Increased privacy and easy access should be at the core of such interventions.
Improving access to mental health care through innovative and scalable screening and treatment approaches is a core priority of the World Health Organization (WHO), as outlined in the Comprehensive Mental Health Action Plan 2013–2030 [15], and of the European Commission through its Comprehensive Approach to Mental Health [16]. In alignment with these frameworks, Greece, in collaboration with the WHO—supported by the National Recovery and Resilience Plan Greece 2.0—has initiated the reform of its mental health services by accelerating the digital transformation of its healthcare system [17].
Mobile health (mHealth) applications can serve as promising digital tools for screening and follow-up, while simultaneously offering the advantages of privacy and easy access through smartphones. mHealth applications have been developed for a wide range of mental health disorders, providing self-help resources, facilitating referrals to specialised professionals, and supporting timely diagnosis, prevention, and treatment [18].
The usability of mHealth apps for PPD has been investigated by a few studies worldwide, showing promise on their effectiveness [19,20,21]. Technical features proven to increase their effectiveness involve referrals to clinicians in the user’s geographical area, voice narration through the use of an avatar, the option to complete a questionnaire at a later time, summaries of guidance and advice, and the ability to chat with clinicians asynchronously [19,20,21]. Gamification is further linked to increased user engagement and effectiveness [22].
Ultimately, the objective of the current, mixed-methods study was to design and evaluate, via an online survey with women within the first postpartum year, a culturally adapted, alpha version of an mHealth app designed to support user awareness, self-monitoring, and potential identification of symptoms of PPD in Greece. To date, no such applications exist in Greek. This study is part of a larger project currently under publication; earlier findings (not yet published) revealed that Greek women with PPD expressed willingness to use an mHealth application for support, should one be available. The methodological approach of designing, developing and evaluating key features of the application is presented below.
2. Materials and Methods
2.1. Smartphone Application “HeartHabit”—Alpha Version
The alpha version of the “HeartHabit” mHealth application was developed through a collaboration between departments of computer science, psychology, and social work across two Greek institutions. The development process was informed by an agile methodology framework [23], the Patient and Public Involvement and Engagement (PPIE) approach [24], and the relevant literature on mHealth applications. Agile methodology is an iterative and flexible approach to project development that emphasises continuous feedback, incremental progress, and responsiveness to user needs [23]. Agile approaches prioritise collaboration, rapid prototyping, and adaptive planning over rigid, linear processes [23]. In the context of digital health and social interventions, agile methodology supports the ongoing refinement of tools and procedures through repeated cycles of development, testing, and evaluation, allowing for timely adjustments based on user input and emerging findings. Combining this with the PPIE approach ensured an inclusive design methodology, which was the objective of the survey and is analysed in Section 2.3 and Section 2.4.
More specifically, validated diagnostic questionnaires and suggestions of prevention tools were provided by the psychologist and social worker team to the software developer team for digital implementation. In parallel, optimal features of mHealth apps were identified in the relevant literature. Following iterative meetings for requirement gathering as per the agile methodology [23], key features of the alpha version of the app were determined. Implementation of most key features was also based on agile development principles [23], with the developer team building parts of the app in cycles and at the end of each iteration recording the psychologist and social worker team’s feedback.
Due to limited evidence about Greek mHealth applications, we combined the agile evaluation framework [23] with the PPIE one, involving end users mid-development via the current study. The reported pilot evaluation will shape the main features of the app while capturing feedback on what is currently implemented.
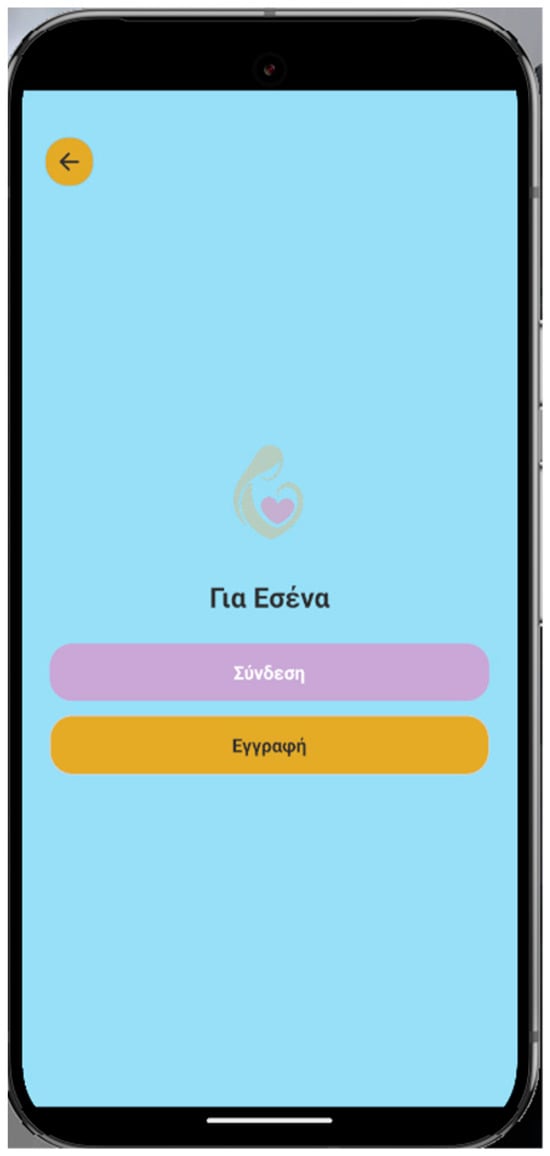
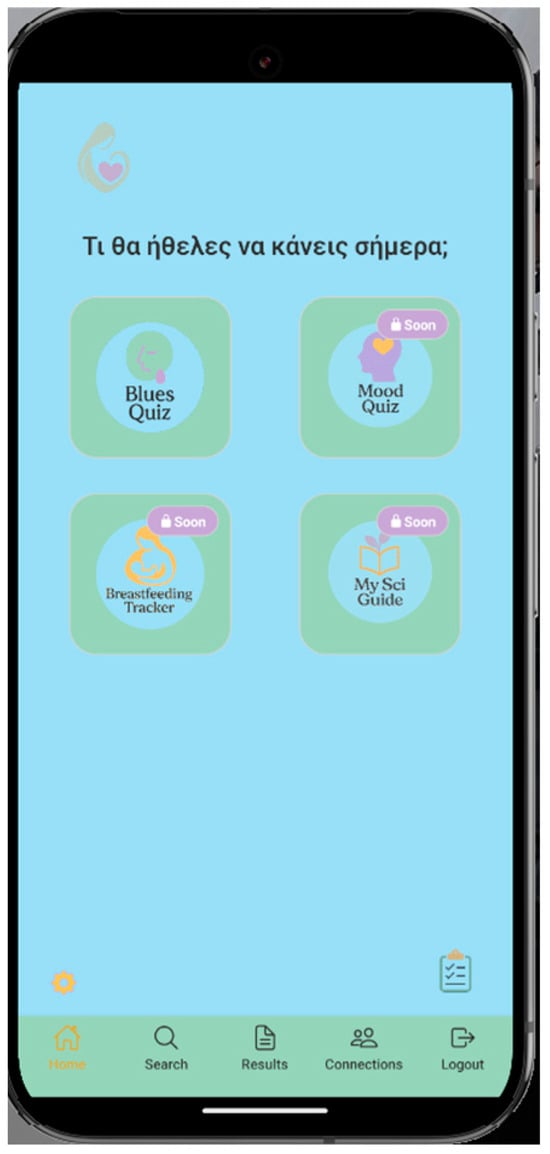
The main features of the “HeartHabit” app include integration of validated diagnostic questionnaires in a gamified format, such as the “Blues Quiz” based on the Edinburgh Postnatal Depression Scale (EPDS) [25], connection with health professionals, breastfeeding and mood tracking modules and an AI-based advisory chatbot (“MySci Guide”). Registration and login options are also implemented. A health professional profile is also incorporated, allowing registered health professionals to receive patient information and notifications about their progress and intervene accordingly in real life.
The system architecture prioritises security and General Data Protection Regulation (GDPR) compliance, using cloud-based encrypted data storage [26]. For the registration and login for both profiles (mother and health professional), email verification is a requirement, allowing additional security via 2-factor authentication.
The colour palette of the application was determined based on literature reviews, colour theory and WCAG guidelines [27]. App colours are proven to strongly impact user appeal, engagement and tool acceptance [28,29]. Light blue and light green were chosen, linking to increased visibility of all screen elements and a stress-release effect on the user [30]. This combination aligns with colour theory principles about pastel colours inducing calmness and colour harmony, promoting visual consistency and focus [31]. As per the WCAG guidelines, the text-to-background contrast ratio requirements were met for both normal and large text, ensuring accessibility [27].
For the online evaluation of the app, a 4 min walkthrough video was recorded, showcasing in detail the primary features of the app, including those that are still under development. The video included the registration and login functionalities, completing the gamified EPDS “Blues Quiz”, demonstrating the award system for regular completion and motivating feedback, the breastfeeding and mood trackers, and the AI-based advisory chatbot “MySci Guide”. The functionality of connecting with a health professional was also displayed, including showing the professional’s profile with the corresponding notification about a patient and the information they would receive.
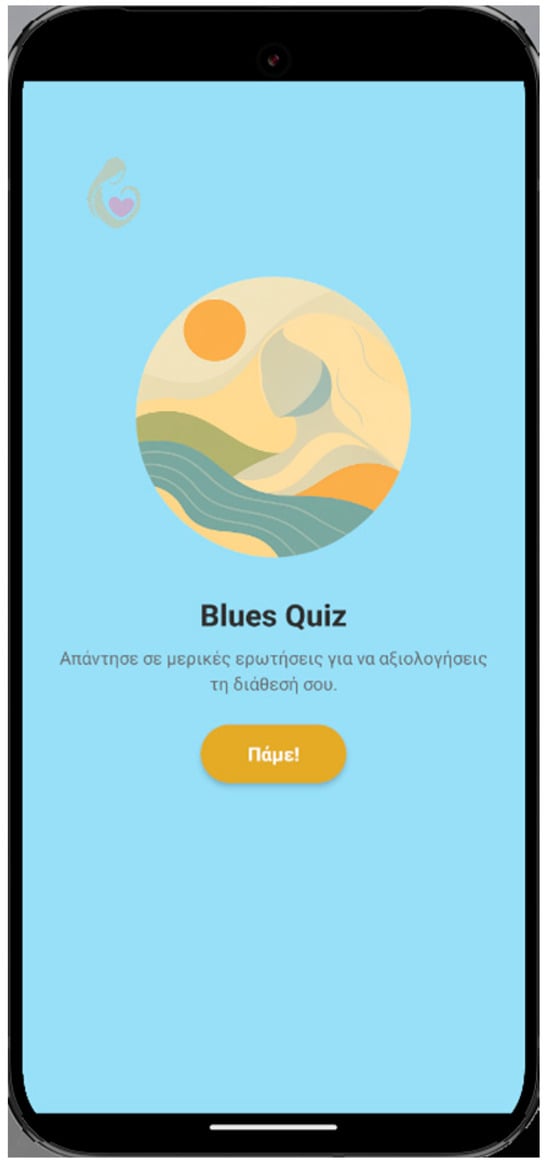
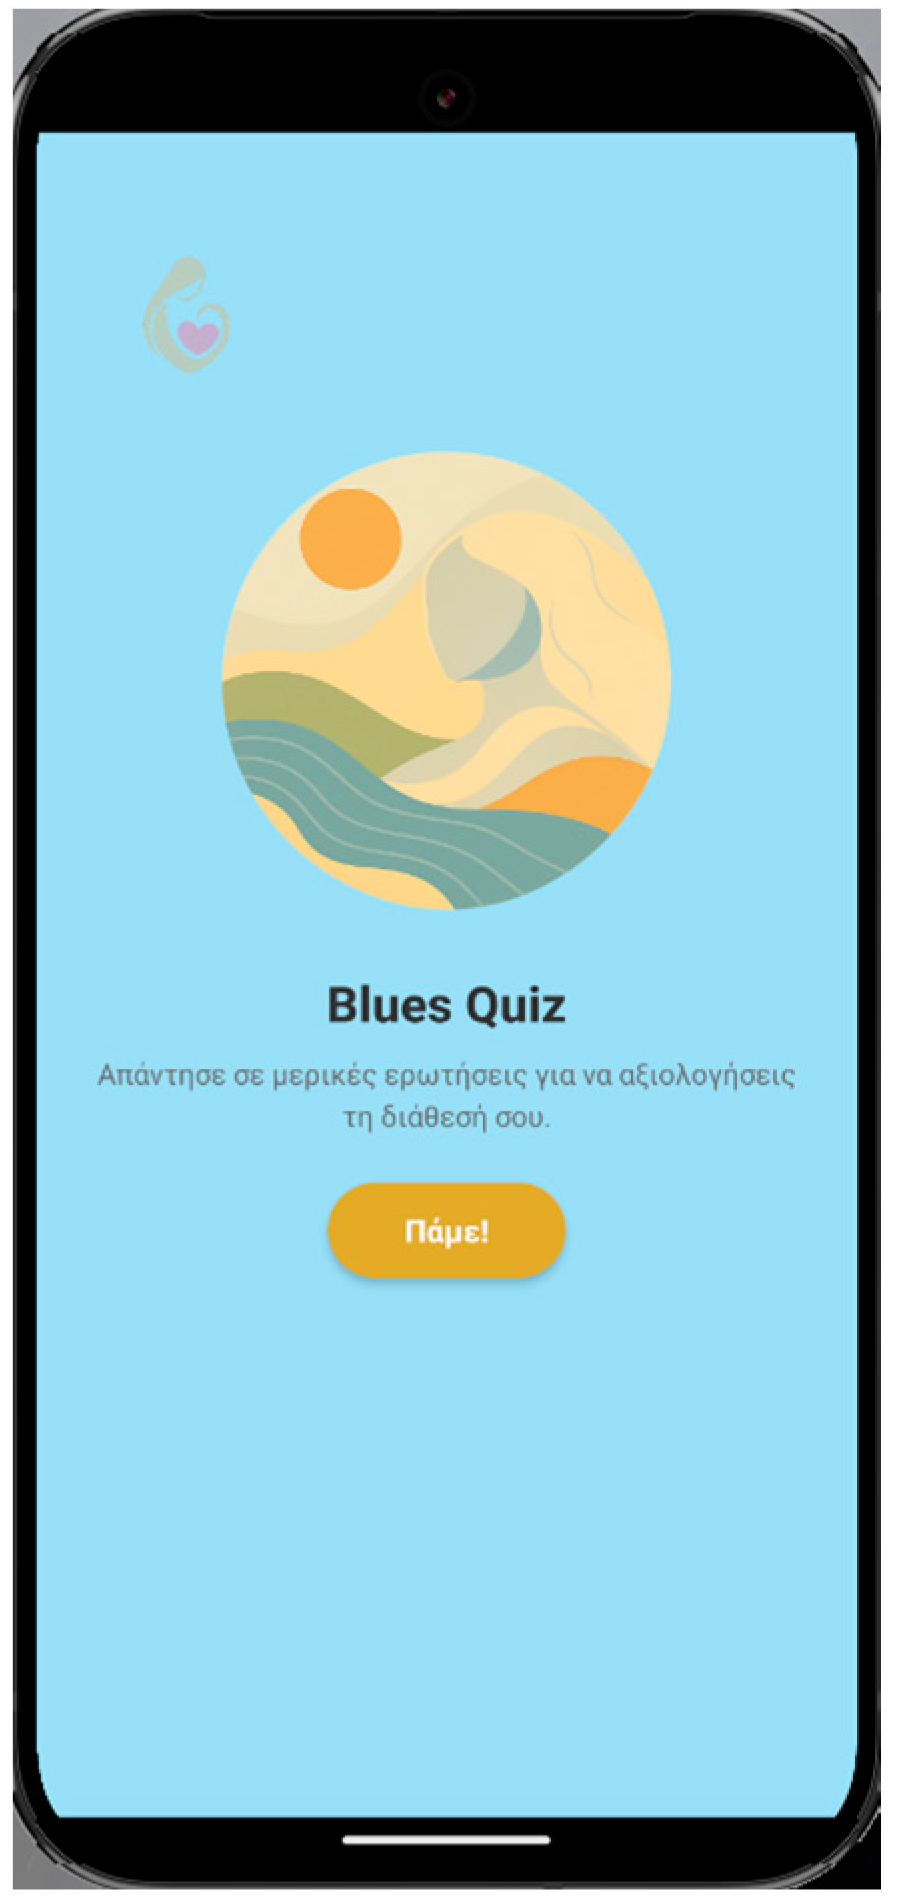
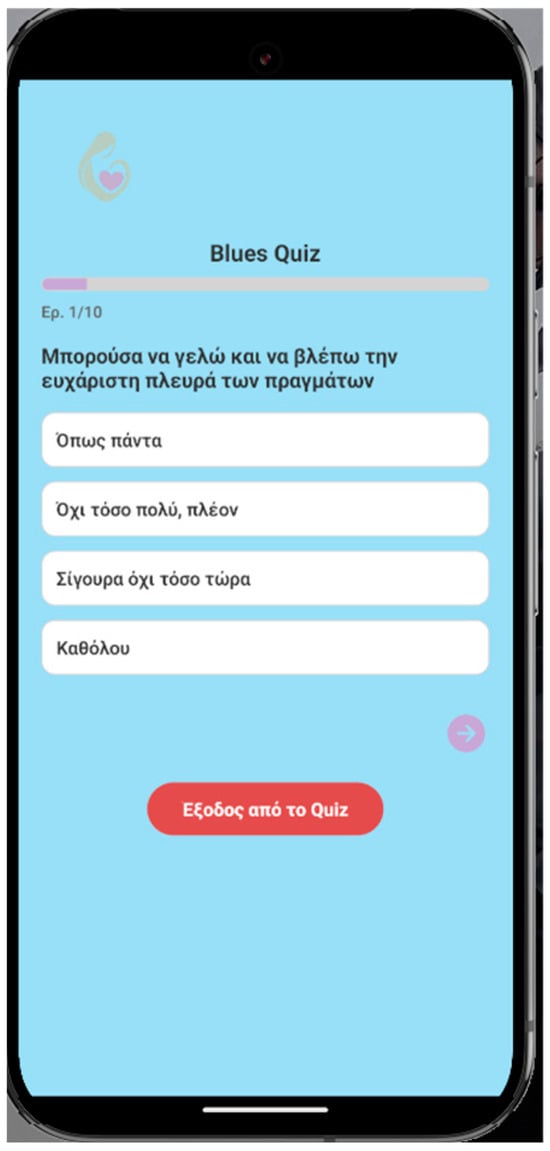
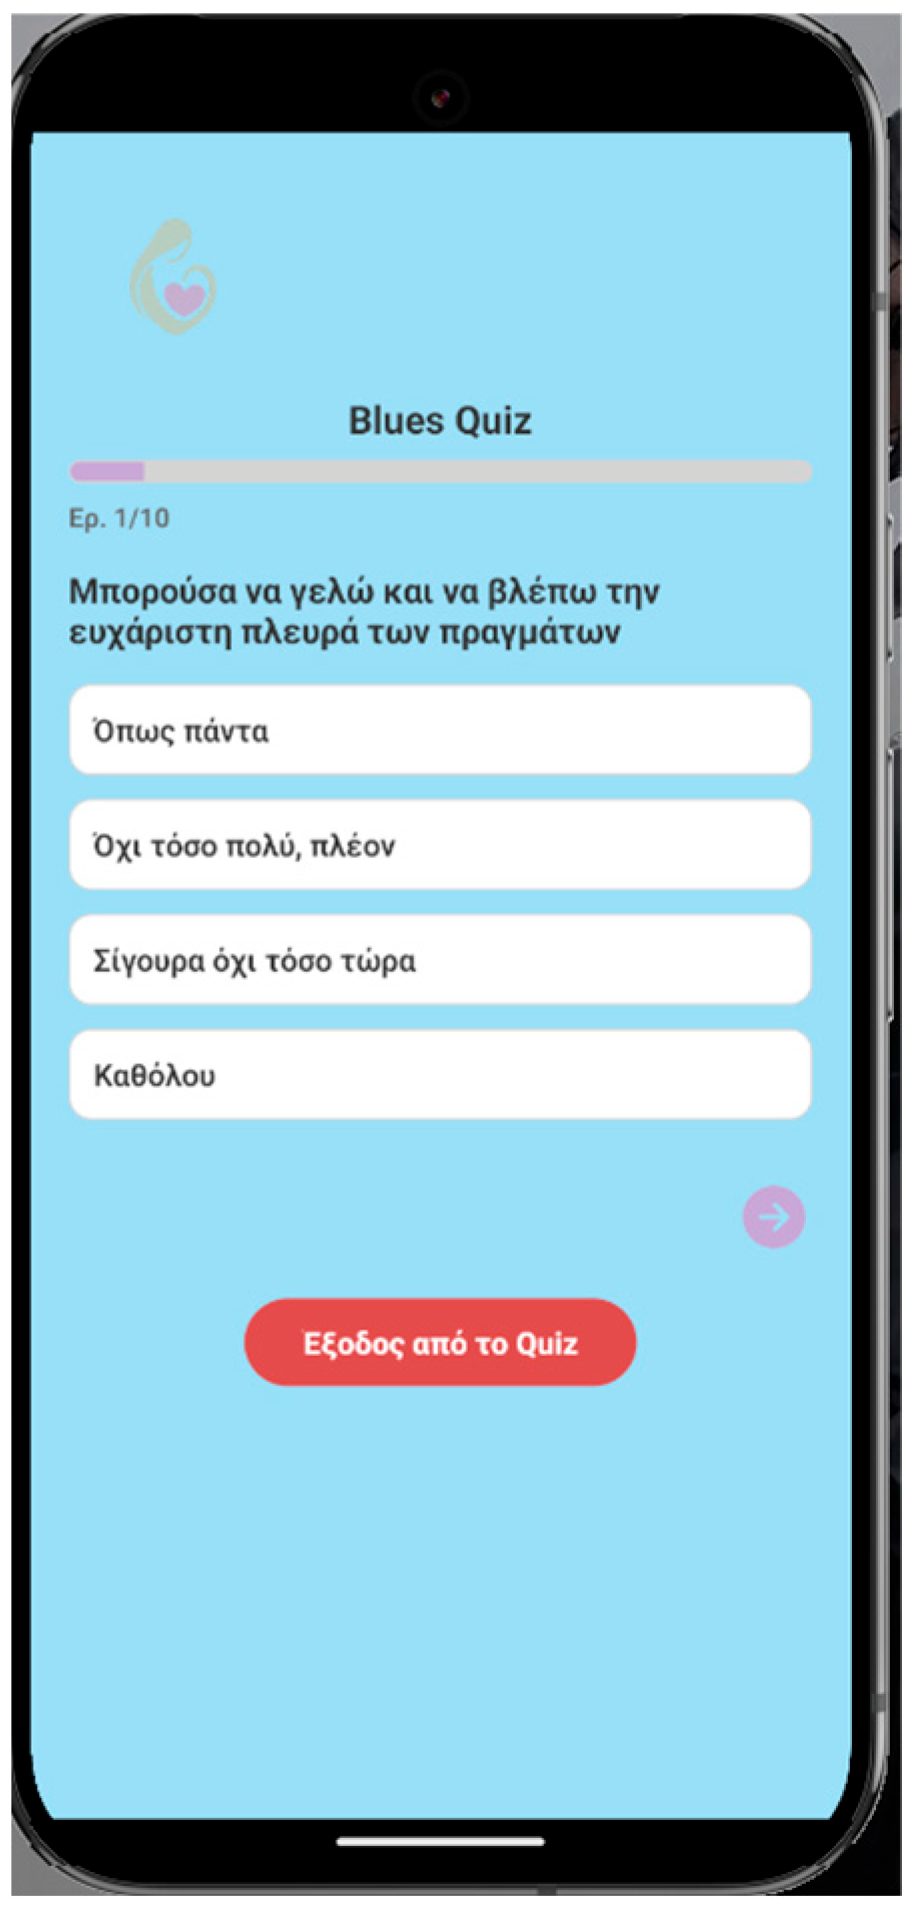
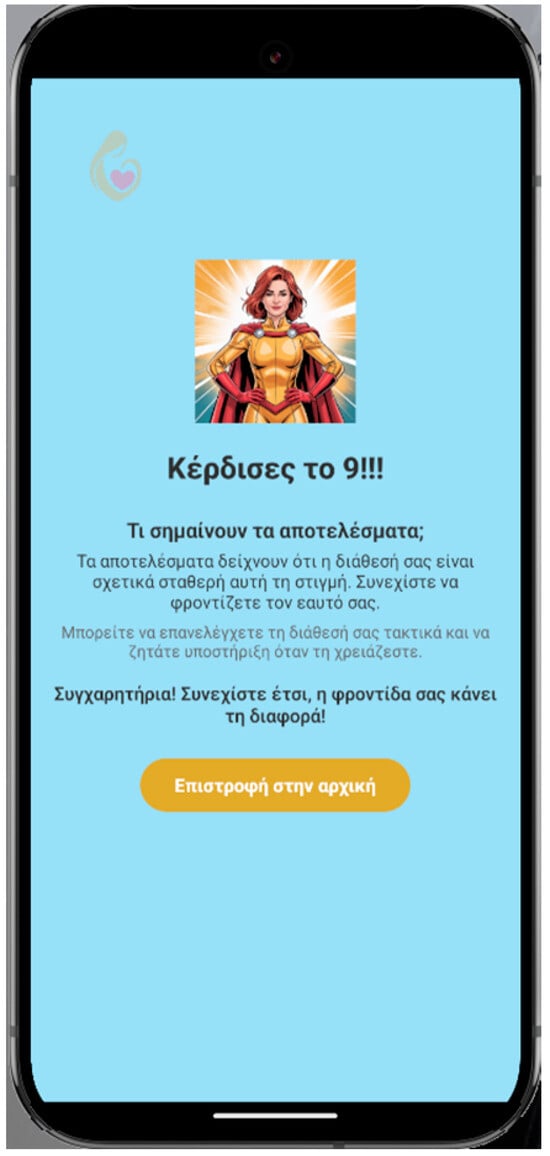
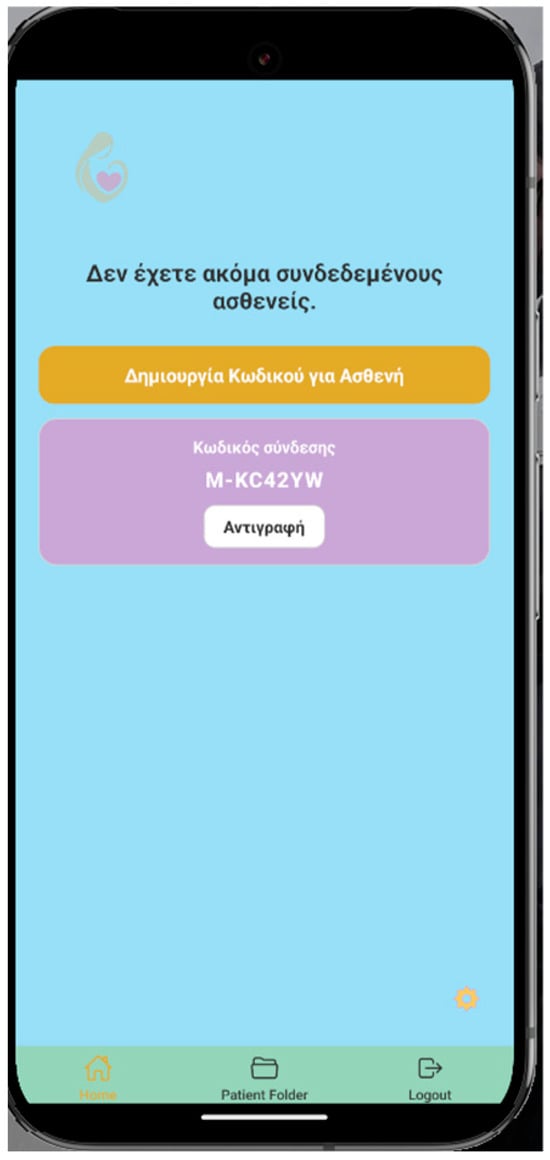
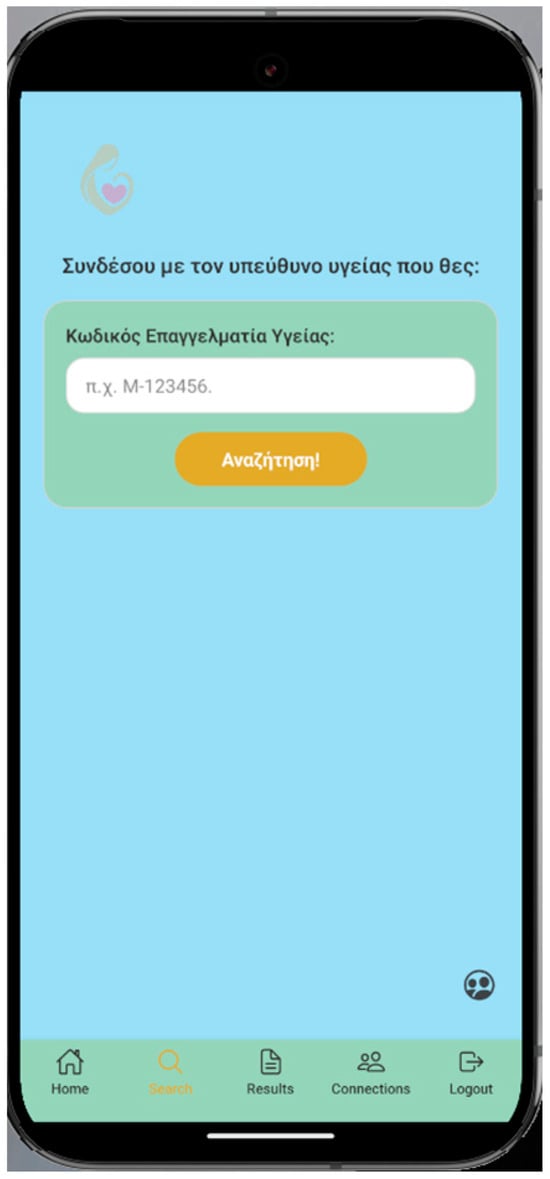
Screenshots of the “HeartHabit” app are presented below (Figure 1, Figure 2, Figure 3, Figure 4, Figure 5, Figure 6 and Figure 7).
Figure 1.
HeartHabit login and registration screen (user: mothers).
Figure 2.
HeartHabit home screen (user: mothers).
Figure 3.
Blues Quiz start screen.
Figure 4.
Question screen of the Blues Quiz.
Figure 5.
Results screen of the Blues Quiz.
Figure 6.
Code generation (to provide patients with) screen of healthcare professionals.
Figure 7.
Health professional search screen of mothers.
2.2. Software and Equipment
The mHealth App was developed using React Native (v0.76.9, Menlo Park, CA, USA) and Expo (v52.0.47, Palo Alto, CA, USA) in Visual Studio Code (v1.95, Redmond, WA, USA) and Android Studio (Giraffe | 1 March 2022, Mountain View, CA, USA), with backend services powered by Supabase (v2.47.0, San Francisco, CA, USA). The walkthrough video was recorded using OBS Studio (v30.2.3, OBS Project, Sheridan, WY, USA). Participants used their personal devices with internet access to view the walkthrough video for the purposes of this evaluation.
2.3. Sample and Recruitment
Participants were recruited via purposive and convenience sampling. The inclusion criteria for participating in the online survey were (1) having an age of 18 years old or older and (2) having given birth within the past year. These criteria were determined to ensure relevance to the target population of the application. No formal exclusion criteria were applied beyond not meeting the inclusion criteria. This approach was adopted due to the exploratory and pilot nature of the study, aiming to maximise participation and capture a broad range of user experiences. The study was advertised on social media accounts of the researchers’ institutions and an internal study advertising platform. The advertising text asked for voluntary participation in a survey about the evaluation of a smartphone app designed to support prevention and diagnosis of PPD. Individuals who were interested in taking part clicked on the link provided to open the survey.
Of the potential participants, 34 provided consent to complete the study and started to provide data. Of the 34 participants, 4 withdrew at some point during the survey and the remaining 30 completed the survey.
2.4. Procedure of Pilot Evaluation
This study employed a mixed-methods, cross-sectional pilot design, combining quantitative and qualitative approaches to evaluate the usability, quality, and perceived acceptability of the “HeartHabit” application.
Potential participants were first presented with the study information sheet before confirming eligibility and providing informed consent. Participants were asked to complete the survey in one sitting. The survey required approximately 20 min to complete. To ensure data quality, several measures were implemented. First, the survey software did not allow participants to proceed if they did not complete main items of the survey (except for sensitive items, such as items of psychometric evaluations and mental health background), reducing missing data. Second, participants were not allowed to submit the survey more than once, minimising duplicate responses. Third, the use of a standardised walkthrough video ensured that all participants were exposed to the same application features prior to evaluation, enhancing consistency in responses. Finally, data collection was conducted anonymously, reducing response bias and encouraging honest reporting. The survey was divided into five parts and was administered in Greek for cultural relevance. Parts 3, 4 and 5 constitute the core app assessment. The app evaluation was based on two conceptual aspects—system usability and app quality—ensuring a holistic assessment and perceived acceptance of the “HeartHabit” mHealth app. To achieve this, the System Usability Scale (SUS) was employed for measuring usability and the Mobile App Rating Scale (MARS) for assessing app quality specifically for mHealth apps [32,33].
Part 1: Demographic Characteristics
The first part was the collection of demographic information, such as gender, age, delivery information, mental health background, access to social support, internet access, and familiarity with mHealth apps and technology. The item “Language” (Γλώσσα) in the original Greek survey aimed to capture the participants’ primary language as PPD applications are language-sensitive; however, this may not be fully explicit in translation in other languages, such as English.
Part 2: Mood and Stress Evaluation
The second part was focused on assessing the mood and stress states of participants at the period of taking the survey (in the past 1 to 2 weeks). Mood was evaluated via the validated Greek version of the EPDS [34,35]. The EPDS was developed by Cox et al. as a self-report measure to identify women who may experience PPD [25]. It consists of 10 items relating to the past 7 days, and each answer is given a score of 0–3. The maximum score is 30, with cut-off values of 10 and above to suggest possible or probable depression. The EPDS is widely validated and demonstrates good reliability and sensitivity for postpartum populations.
Stress was evaluated via the validated Greek version of the General Anxiety Disorder-7 (GAD-7) scale [36]. The GAD-7 was designed to measure anxiety severity in the last 2 weeks, and it consists of 7 items tracking the frequency of stress-related symptoms (Likert scales of 0—not at all to 3—nearly every day) [37,38]. Scores are categorised as 0–4: minimal anxiety; 5–9: mild anxiety; 10–14: moderate anxiety; and 15–21: severe anxiety. The GAD-7 has demonstrated strong reliability (Cronbach’s α > 0.85) and validity in both general and perinatal populations. Previous validation studies have reported good internal consistency (Cronbach’s α > 0.80) for both instruments specifically in Greek-speaking samples [34,36].
Part 3: Usability Evaluation
In the third part of the survey, participants were asked to watch the walkthrough video of the app on their personal device, as many times as they wished. The video was available through a link embedded in the survey. In the next step, a validated Greek version of the SUS was presented, allowing participants to assess the app usability [37]. The SUS was developed to evaluate the usability of electronic office systems and is widely employed in usability engineering [32]. It consists of 10 items about usability attitudes, each with a Likert-scale answer scoring from 1 “strongly disagree” to 5 “strongly agree”. Scores are converted to a total score ranging from 0 to 100, with higher scores indicating better usability. The SUS has demonstrated strong reliability (Cronbach’s α ≈ 0.9) and validity across a wide range of digital systems.
Part 4: Quality and User Experience Evaluation
The fourth part consisted of both quantitative and qualitative measures. First, participants were asked to complete a stand-alone section (section E: App Subjective Quality) of the validated Greek version of the user Mobile Application Rating Scale (uMARS) [39]. The uMARS was developed to assess the quality of mHealth apps [33]. It consists of 6 sections (engagement, functionality, aesthetics, information, app subjective quality and perceived impact), each with a group of Likert-scale items, scoring from 1—negative attitudes/strong disagreement to 5—positive attitudes/strong agreement, with higher scores indicating better perceived app quality. The sections about engagement, functionality, aesthetics and information were adapted into open-ended questions, including a custom part about participants’ desired features to be implemented, enabling rich feedback about the app’s features and informing its design. The uMARS has demonstrated good internal consistency and construct validity in mHealth research.
Part 5: Participant Closing Statements
In the fifth part, participants answered three open-ended questions about their overall perception of the app, whether they would recommend it to other mothers and why/why not, and any other comments or suggestions they wish to add.
Finally, a list of local sources of support was provided at the end of the survey, including contact information, should participants feel distressed or require additional help.
The survey guide can be found in the Supplementary Material.
2.5. Data Analysis
Quantitative analysis of the study was conducted in SPSS, version 29.0.2.0.
For the demographics, descriptive statistics were used to present an overview of participant characteristics. The EPDS, GAD-7, SUS and section E of the uMARS questionnaire were analysed as per the scoring guidelines for each questionnaire [34,37,39]. Descriptive statistics were used to provide mean scores per questionnaire, and results were interpreted using established cut-off thresholds. Given the exploratory nature of the study and the modest sample size (n = 30), analyses were primarily descriptive.
Qualitative analysis was conducted by the first author using Microsoft Excel spreadsheets. Open-ended responses from Parts 4 and 5 of the survey were analysed using Framework Analysis [40]. This structured approach was selected due to its suitability for applied health research and its compatibility with both deductive and inductive analysis. The process involved familiarisation with the data, development of an analytical framework, systematic coding of responses, and charting data into a thematic matrix to facilitate comparison across participants. Initial coding was deductively guided by the predefined uMARS domains, as shown in Table 1 [39]; however, there was substantial conceptual overlap between the engagement, aesthetics, and functionality domains. The themes were, therefore, restructured to better reflect participants’ integrated user experiences. In addition, inductively derived subthemes were incorporated to capture insights emerging directly from the data.
Table 1.
Domains of the user Mobile Application Rating Scale.
To enhance analytical rigour, coding decisions were reviewed and refined iteratively by another researcher of the team, and an audit trail of framework development was maintained. Data saturation occurred after the 16th participant’s input was coded. The matrix produced by the analysis included the original quotations in Greek. For reporting purposes, quotations were also translated from Greek into English by the first author and reviewed by the rest of the team for accuracy.
Where applicable, qualitative patterns were explored in relation to depression and stress severity and usability ratings of each participant to support an integrated approach. No formal inferential comparisons were conducted due to the exploratory design of the study.
2.6. Ethical Approval
Ethical approval for the study was granted by the Metropolitan College Research Ethics Committee (Ref.: 2020-8466-17087) on 3 December 2025.
2.7. Use of GenAI Acknowledgement Statement
During the preparation of this manuscript, the authors used ChatGPT (v5.3) for the purposes of generating the visuals of the graphical abstract, and the text was provided as an input. The authors have reviewed and edited the output and take full responsibility for the content of this publication.
3. Results
3.1. Participants’ Characteristics
A total of 30 participants completed the survey. The sample consisted primarily of Greek women (90%, n = 27) residing in urban areas (73.3%, n = 22), with a mean age of 31 years. All participants (100%, n = 30) reported speaking Greek fluently and were able to complete the survey in Greek. Infants’ ages of participants (and, subsequently, time since delivery) were evenly distributed across the first postpartum year. Slightly more than half of participants (≈57%, n = 17) were multiparous.
Most participants reported high familiarity with mobile applications (≈73%), although 70% had no prior experience using a mental health app. The majority typically accessed the internet via Android devices (≈83%, n = 25).
Psychological screening indicated that, while mean depressive symptoms (M = 7.5, SD = 3.9) were below the clinical cut-off on the EPDS, one-third of participants (≈33%, n = 10) reported elevated depressive symptoms (≥10). In contrast, anxiety levels assessed using the GAD-7 scale were notably high, with approximately 83% of participants (n = 25) scoring within the clinically significant range (≥10), suggesting that anxiety symptoms were prominent within the sample and indicative of potential GAD.
An overview of the characteristics of participants is presented in Table 2. Mood and stress evaluation results are presented in Table 3 and Table 4, respectively.
Table 2.
Descriptive data of participants.
Table 3.
Edinburgh Postnatal Depression Scale results of participants’ mood evaluation.
Table 4.
General Anxiety Disorder 7 scale results of participants’ stress evaluation.
3.2. Usability Evaluation
The mean SUS score was 83.7 (SD = 4.8), with scores ranging from 75 to 93, indicating overall good-to-excellent usability. Based on established SUS grading thresholds, 63.3% of participants rated the app within the “Excellent” range (>80.3), while 36.7% rated it as “Good” (68–80.3). No participants rated the app below the acceptable usability threshold (68), indicating consistently high perceived usability across the sample.
3.3. Quality and User Experience Evaluation
The mean score of the App Subjective Quality variables for the “HeartHabit” as seen in section E of the validated Greek version of the uMARS was 8.5 (SD = 1.1) out of 10, with a minimum of 5 and a maximum of 10 [39].
Further qualitative assessment of the app, via Framework Analysis, revealed four main themes [40], the first three directly associated with the uMARS domains and the fourth inductively emerged from the data (including Part 5 of the survey) [39]. The themes mapped to (1) engagement and functionality, (2) aesthetics, (3) information quality, and (4) privacy and data protection. Each theme was further linked to inductively derived subthemes, as shown in Table 5, where the final framework is presented.
Table 5.
Framework of analysis with themes and subthemes.
3.3.1. Engagement and Functionality
Practical Usability
Practicality in use, including easy navigation and intuitive structure, was identified as a core advantage of the application by most participants: “Many mothers need something immediate and easy. I consider it a good tool so you’re not left alone with your thoughts… I found it practical for everyday use.” (P5, 37 years old; minimal depressive symptoms; severe anxiety); “The navigation was quite smooth. It didn’t take much time, and that’s important.” (P8, 31 years old; minimal depressive symptoms; mild anxiety). It was particularly reported to promote daily uptake, even in uncomfortable settings, such as a mother holding their baby while navigating the application, “It was practical, especially when I’m with the baby.” (P1, 31 years old; minimal depressive symptoms; moderate anxiety), or when using the application while extremely tired, “It gives the impression that I can use it even when I’m tired.” (P23, 30 years old; possible depressive symptoms; moderate anxiety). Quick registration was considered as another practical functionality.
Suggestions for enhancing usability involved clearer menu labels and access to content on demand. For example, the addition of a search function was proposed to improve efficiency: “There should be a search function so I can quickly find sections.” (P9, 38 years old; minimal depressive symptoms; moderate anxiety). Advancing the feature of the AI-agent (“MySci guide”) to facilitate chat sessions for educative purposes was also perceived practical and time-saving: “I would like it if it offered practical suggestions.” (P28, 31 years old; minimal depressive symptoms; moderate anxiety); “I’m interested, especially if it remembers my preferences.” (P11, 29 years old; possible depressive symptoms; severe anxiety). An introductory tutorial at first use was also proposed by a few participants to assist with the familiarisation with the app: “A very short tutorial at the beginning would be helpful.” (P27, 34 years old; possible depressive symptoms; severe anxiety).
Overall, the support the “HeartHabit” app could offer was seen as time-effective and flexible (accessed easily at home), especially when formal support would be hard to receive timewise: “…especially for those who don’t have time to seek help immediately. It’s something you can do from home when your schedule is demanding.” (P17, 31 years old; minimal depressive symptoms; moderate anxiety).
Personalisation Features
Personalisation was perceived to be important for sustained engagement. Most participants acknowledged the value of adaptive reminders and notifications about their progress, tasks and goals: “I would like to be able to customise the notification times and frequency.” (P4, 36 years old; minimal depressive symptoms; moderate anxiety); “(Personalisation is)…quite useful, especially for reminders and goals.” (P9, 38 years old; minimal depressive symptoms; moderate anxiety). Personalising the content was perceived necessary as postpartum needs vary over time, which was thought to be partially facilitated by the feature of the AI chatbot.
Connectivity and Integration
Connectivity was another functionality perceived to be critical for the app. More specifically, connection with a health professional was endorsed by most participants, due to its potential to offer tailored support and medical supervision: “The fact that I will have an overview (of current mental health state), as well as my doctor.” (P23, 30 years old; possible depressive symptoms; moderate anxiety). It was, however, discussed by a few participants that it should not replace formal, in-person support and for this to be explicitly acknowledged within the app.
Functionalities such as forums and chatting with other mothers using the app and an SOS emergency call button accompanied by contact details of relevant helplines were additional suggestions to enhance the connectivity of the app.
Self-Regulation and Coping Support
Self-regulation tools were particularly valued. Mood evaluation and progress visualisation were described as motivating by most participants: “I liked it—what won me over was the ability to track my progress, as it reduced my anxiety in that moment.” (P9, 38 years old; minimal depressive symptoms; moderate anxiety). They were further reported to increase awareness by helping users to identify mental and emotional issues: “…connection with my mental health and the new emotions I’m experiencing.” (P26, 33 years old; minimal depressive symptoms; moderate anxiety).
Most participants underscored that the app would be an important tool for providing support: “I would see it as an ally in everyday life.” (P25, 21 years old; minimal depressive symptoms; mild anxiety). A few participants proposed that it could function as a first point of access to support: “It can also function as a first step before seeking help.” (P30, 38 years old; minimal depressive symptoms; moderate anxiety). Several participants suggested that it could operate as adjunctive to formal therapy schemes: “I would recommend it as a complementary tool alongside professional support.” (P20, 36 years old; probable depression; severe anxiety).
Relaxation exercises and guided coping strategies were viewed as beneficial additions by some participants. Mood logging was thought to operate as a release mechanism and would be a desirable feature to implement further. Overall, engagement was closely tied to functional clarity and psychological support features.
3.3.2. Aesthetics
Soothing Visuals
The app’s visual design was widely perceived as calming and emotionally supportive. Most participants frequently referred to the use of soft colours and a balanced, calming layout. One participant commented, “I liked the colours; they were calm and clean.” (P5, 37 years old; minimal depressive symptoms; severe anxiety), linking aesthetics to emotional comfort.
User-Friendliness
The layout was described as simple and pleasant by the majority of participants, contributing to user-friendliness: “The design was user-friendly and not tiring to look at.” (P16, 25 years old; possible depressive symptoms; severe anxiety). The fonts throughout the app were additionally endorsed by most participants, being nice and matching with the app’s scope. A few participants suggested that would like more contrast on the buttons’ colours in relation to the app’s background, increasing visual clarity: “I would like a bit more contrast on some buttons.” (P10, 33 years old; minimal depressive symptoms; mild anxiety). A few participants also noted that they would prefer more spaces in between text in the quiz for a more balanced layout. Finally, several participants noted that the tone in wording and the presentation of information were user-friendly and non-judgemental, being well-suited for an mHealth app: “(The app was…) Very positive overall—simple, user-friendly, and meaningful.” (P12, 31 years old; possible depressive symptoms; moderate anxiety).
Professional Design
The app’s design was described as professional by some participants, stating also that this reinforced trust in the app’s purpose: “(The app was…) Professional yet warm.” (P13, 25 years old; possible depressive symptoms; moderate anxiety). The well-organised content and simplicity in the visuals were aspects, as mentioned by a few participants, that contributed to the credibility and professional look of the app.
3.3.3. Information Quality
Clarity of Information
A large proportion of participants found the information clear and accessible. As one noted, “Almost everything was understandable.” (P15, 28 years old; probable depression; severe anxiety). Content was described as written in simple language, without unnecessary complexity.
Graphs for a depictive presentation and clear overview of mood logs and clear data safekeeping guidelines were aspects a few participants reported as necessary to implement in the future.
Relevance of Content
Relevance was perceived by a great part of participants as another critical factor of the app’s information quality. More specifically, they commented on the content being relevant to lived postpartum experiences to a great degree, speaking to both mental and emotional needs of a new mother. One participant stated, “(The content was…) Very useful, as needs change from day to day.” (P4, 36 years old; minimal depressive symptoms; moderate anxiety). A minority highlighted that mood evaluation could induce feelings of stress and guilt due to addressing very relevant points regarding mental health states.
A few participants suggested expanding content variety, such as sleep routine suggestions for the baby, or including additional features such as the AI chatbot.
Perceived Credibility
Perceived credibility was linked to the app’s professional tone and its apparent grounding in evidence-based knowledge. Connection with medical professionals was unanimously believed to increase the app’s credibility. The academic reference included in the mood evaluation quiz was considered to increase trustworthiness by several participants: “It seemed trustworthy, especially if it clearly states who developed it.” (P11, 29 years old; possible depressive symptoms; severe anxiety). Some participants also suggested that they would like to see such academic references in all the app’s content, ranging from quizzes to parental tips. App licences and certificates were another aspect thought essential to be mentioned by a few participants. Finally, auditing of the forum, if implemented, and transparent data policy and safety procedures, such as email confirmation during registration or data encryption, were further deemed necessary and factors of credibility: “(Factors are…) Certifications, collaboration with healthcare professionals, and transparency.” (P1, 31 years old; minimal depressive symptoms; moderate anxiety).
3.3.4. Privacy and Data Protection
Transparency and Data Governance
Privacy emerged as a critical theme influencing trust and acceptability. Several participants stressed the importance of transparency in data handling. One participant stated, “There should be clear information about who has access (… to data).” (P19, 34 years old; minimal depressive symptoms; moderate anxiety), in line with the perceived concerns of some participants about data governance. Transparency in data safekeeping by clear statements within the app was also considered essential by a few participants: “It should explain in simple terms how the data are protected.” (P9, 38 years old; minimal depressive symptoms; moderate anxiety).
User Control and Data Autonomy
User control was strongly emphasised. The majority of participants viewed the functionality of deleting personal data as essential: “I want to be able to delete my data whenever I choose.” (P16, 25 years old; possible depressive symptoms; severe anxiety). Full account deletion options were also considered important for autonomy by a few participants.
Anonymity and Identity Protection
Anonymity was linked to emotional safety, particularly when discussing sensitive mental health concerns, as noted by some participants. A few participants also stated that they would like to be assured that the app was in compliance with the GDPR guidelines and that their identity was protected [26]: “Clear terms and conditions, GDPR compliance.” (P3, 25 years old; minimal depressive symptoms; moderate anxiety). Data encryption and minimisation were additional elements most participants considered important for protection of their identity: “It should not request more information than necessary.” (P15, 28 years old; probable depression; severe anxiety).
4. Discussion
This pilot study followed a mixed-methods, cross-sectional design and examined the acceptability of the alpha version of an mHealth application (“HeartHabit”) intended to support user awareness, self-monitoring, and potential identification of symptoms of PPD among 30 mothers in Greece (being within the first postpartum year). Overall, usability ratings were very high (mean SUS = 83.7), and qualitative feedback emphasised the app’s potential as a practical, emotionally supportive adjunct to care. However, it is important to note that the evaluation was based on a walkthrough video rather than direct interaction with the application. As such, participants’ responses reflect anticipated use and perceived usability rather than lived interaction with the system. At the same time, nearly one-third of participants reported elevated depressive symptoms (EPDS ≥ 10), and a large majority exhibited clinically significant anxiety (GAD-7 ≥ 10), highlighting both the clinical relevance of this user group and the need for a validated, safe app design, distress protocols and referral pathways.
Indeed, relevant research suggests mHealth apps should be carefully assessed and integrated into clinical care settings, with end users actively involved. This justified the iterative design and evaluation methodology of the “HeartHabit” app with real-world users and validated acceptability instruments [28,41]. Our mixed-methods design ensured that both quantitative, usability data and qualitative insights were captured for this population, feeding directly into its development in an iterative and inclusive manner as per agile and PPIE principles [23,24].
The usability score observed in this study (mean SUS = 83.7) falls within the “excellent” range and is consistent with findings from prior mHealth PPD applications. For example, previous studies evaluating smartphone-based interventions for PPD have reported high levels of user acceptability and perceived usability, particularly when applications incorporate user-centred design, self-monitoring tools, and clinician integration [19,20,21]. The high usability observed in the present study may reflect similar design priorities, including simplicity, practical functionality, and emotional support features tailored to postpartum needs.
Practical usability and user-friendliness were among the dominant sub-themes of the qualitative analysis, underscoring the importance of smooth navigation, time-effectiveness and overall practicality during mHealth app use in PPD samples. Our findings aligned with prior mHealth research, indicating that well-designed, easy-to-use digital tools can achieve high levels of acceptability among postpartum women and support engagement with mental health self-care [28,42]. These findings can also be interpreted through the lens of the Technology Acceptance Model (TAM), as usability and perceived usefulness emerged as central determinants of acceptability [43].
Participants also repeatedly described the app as an “ally” in everyday life, valuing features such as mood assessment and progress tracking. Connection with a healthcare professional has additionally emerged as a key feature, increasing the app’s credibility and ensuring supervision. These functionalities contributed to the majority of participants recommending the app as a relevant, assistive tool to formal care or as at-home support when access to treatment would not be possible. These findings are consistent with previous studies showing that self-monitoring and micro-interventions delivered through mobile technologies can reduce barriers to care, enhance emotional awareness, and facilitate symptom self-management in perinatal populations [28,42,44]. Similarly, the positive user comments observed via the uMARS align with the existing literature on perinatal mHealth interventions, where engagement, personalisation, and perceived relevance have been identified as key drivers of user satisfaction and continued use [41,42]. In particular, features such as mood tracking, progress visualisation, and access to professional support—highlighted by participants in this study—have been associated with increased engagement and perceived value in postpartum digital mental health tools [20,21].
Privacy and data protection emerged as another major domain affecting the app’s acceptability. Participants repeatedly requested clear data governance, the ability to erase personal data or accounts, data minimisation and assurances regarding compliance with the GDPR [26]. Such concerns are consistent with the existing literature, indicating that privacy, transparency, and data control are central determinants of user trust and engagement with digital mental health tools [41,45,46]. For mental health applications addressing sensitive postpartum experiences, these considerations should be treated as core design requirements rather than optional features, ensuring responsible implementation. It should be noted that the present evaluation focused on users’ perceptions of privacy rather than the implementation of technical privacy-preserving mechanisms. Nevertheless, future iterations should consider the integration of formal privacy-preserving approaches, such as k-anonymity and optimisation-based anonymisation techniques, to mitigate re-identification risks in sensitive health data [47].
Similarly, the AI-based chatbot (“MySci Guide”) presented in this study as a conceptual feature was highly endorsed by participants, but as no real interaction occurred, issues related to model architecture, safety, and clinical validation were outside the assessment objectives of this study. Nevertheless, integrating AI into mental health applications requires careful attention to ethical and safety considerations. Future development should include appropriate governance frameworks, clinical oversight, and rigorous real-world validation prior to deployment.
Another important finding is the mismatch between depressive and anxiety symptoms in this sample; while most EPDS scores were below clinical screening thresholds, anxiety symptoms were frequent and often moderate to severe. This may reflect the postpartum period, where heightened worry and adjustment to new caregiving responsibilities are common. The current finding aligns with the literature suggesting that perinatal mental health challenges often extend beyond depression alone and that anxiety symptoms are highly prevalent during the postpartum period [10]. This discrepancy has important implications for the design and scope of such applications. While PPD screening should be included, the findings suggest that addressing anxiety symptoms should be equally prioritised. Features such as stress management tools, relaxation exercises, psychoeducation on anxiety, and tailored feedback could enhance the app’s relevance and effectiveness. Moreover, integrating anxiety-sensitive content (e.g., preference for calming visuals and non-judgemental logging), monitoring and referral pathways could cover the need for such applications to operate as emotionally safe interfaces.
Overall, the findings of this study have important practical implications for the design and implementation of mHealth interventions targeting postpartum mental health. Participants’ emphasis on simplicity, ease of navigation, and time-efficiency highlights the need for tools that can be seamlessly integrated into the demanding routines of new mothers. Features such as quick access, low cognitive load, and flexible engagement appear critical for real-world uptake. The value placed on personalisation and self-monitoring suggests that adaptive, user-responsive features may enhance sustained engagement and relevance. At the same time, the strong emphasis on privacy, transparency, and user control indicates that trust-building mechanisms should be treated as core design requirements, with clear communication of data governance policies supporting adoption and continued use. Participants’ preference for connectivity with healthcare professionals further supports the role of such applications as adjunct tools within hybrid care models. Finally, given the high digital literacy of the current sample, future implementation should prioritise accessibility and inclusivity to ensure usability across diverse user groups. These insights can inform the iterative development and integration of mHealth tools into perinatal care pathways.
Strengths and Limitations
The overall methodology of this study demonstrated efficiency in iteratively assessing an mHealth app, promoting user involvement throughout the implementation. This innovative approach could form a reproducible paradigm for use at any stage of the evaluation cycle of mHealth apps. The use of established and validated measures, including the SUS and standardised mental health screening instruments, strengthens the reliability of the findings. In addition, the Framework Analysis allowed for systematic exploration of participants’ experiences and priorities, offering detailed insights into the design features that may support engagement with digital mental health tools in the postpartum period [40]. Finally, the inclusion of women with varying levels of depressive and anxiety symptoms enhances the clinical relevance of the findings.
While the findings of this study and the priorities that emerged could inform the implementation of similar mHealth apps, certain limitations should be acknowledged. First, the sample size was relatively small (n = 30), and participants were recruited through convenience sampling. This introduces potential selection bias and limits the representativeness of the sample. As a result, the findings may not be generalisable to the broader population of postpartum women, particularly those with differing socio-demographic or healthcare access characteristics. However, given the exploratory, early-stage nature of this study, the sample size is consistent with usability research, where relatively small samples are considered sufficient to identify the majority of usability issues due to diminishing returns in problem discovery [48]. The majority of participants also reported high familiarity with mobile applications, which may have led to more favourable usability ratings. This limits the transferability of findings to populations with lower digital literacy, who may experience different usability barriers or engagement challenges. Second, recruitment via social media and institutional channels may have introduced selection bias towards participants with higher digital literacy and access to online platforms, potentially underrepresenting mothers from rural areas or with lower digital engagement. Third, the evaluation relied on a prototype walkthrough rather than prolonged real-world use of the application, which may have influenced perceptions of usability and engagement, limiting ecological validity. Therefore, the findings should be interpreted as indicative of initial usability and perceived acceptability rather than real-world effectiveness or sustained user engagement. Overall, these factors (sample size, sampling strategy, and participant digital literacy) restrict the generalisability of the findings, which should be interpreted as preliminary and specific to a digitally literate sample.
Fourth, mental health outcomes were assessed using screening tools rather than clinical diagnostic interviews; therefore, the reported levels of depressive and anxiety symptoms should be interpreted as indicative rather than diagnostic. Finally, this pilot evaluation does not allow conclusions about sustained engagement, behavioural change, clinical effectiveness or treatment uptake as it does not evaluate clinical effectiveness, behavioural outcomes, or diagnostic accuracy. The findings are limited to usability and perceived acceptability within an early-stage pilot context. Therefore, conclusions regarding preventive impact and diagnostic performance cannot be drawn. Future research should involve larger and more diverse samples, longitudinal evaluation, and real-world implementation to assess the app’s effectiveness and long-term impact on PPD. The inclusion of partners and healthcare professionals to assess multi-stakeholder utility and design for shared caregiving features could also be explored. Clinical integration pathways should also be implemented further, in alignment with national and international digital mental health strategies, and by producing robust integration protocols and supportive material (including training resources) for clinicians.
5. Conclusions
This pilot study suggested the potential of a mHealth app (“HeartHabit”), culturally adapted to Greek-speaking mothers, to support user awareness, self-monitoring, and potential identification of symptoms of PPD. Emotional and self-regulation tools, practicality in use, soothing visuals, content credibility assurances, connection with healthcare professionals, and privacy and data protection safeguards were elements identified as important for the app’s acceptability and future effectiveness. Its use as adjunctive to formal care or at-home support, when treatment access would be challenging, were recommended by participants. The mixed-methods evaluation approach adopted in this study—combining usability assessment, qualitative insights, and PPIE principles—may offer a useful paradigm for the early-stage, iterative assessment of digital mental health interventions. With continued iterative development, larger-scale evaluation, and robust, clinical integration protocols and training, such tools have the potential to complement existing perinatal services and help address persistent gaps in access to timely mental health support for new mothers.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/app16094173/s1, Survey instrument in Greek.pdf [25,32,34,35,36,37,38,39].
Author Contributions
Conceptualisation: M.E.F., R.S., and D.S.-P.; methodology: R.S., M.E.F., E.A., A.K., and D.S.-P.; software: E.A. and A.K.; data curation: R.S. and D.S.-P.; formal analysis: R.S. and D.S.-P.; investigation: M.E.F., A.K., E.A., and V.E.C.; writing—original draft preparation: R.S.; writing—review and editing: R.S., D.S.-P., and V.E.C.; supervision: D.S.-P. and R.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the by the Metropolitan College Research Ethics Committee (Ref.: 2020-8466-17087) on 3 December 2025.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The raw data supporting the conclusions of this article will be made available by the authors on request.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| PPD | Postpartum depression |
| mHealth | Mobile health |
| WHO | World Health Organization |
| SUS | System Usability Scale |
| uMARS | User version of the Mobile Application Rating Scale |
| EPDS | Edinburgh Postnatal Depression Scale |
| GAD-7 | Generalized Anxiety Disorder-7 |
| PPIE | Patient and Public Involvement and Engagement |
| GDPR | General Data Protection Regulation |
References
- Wang, Z.; Liu, J.; Shuai, H.; Cai, Z.; Fu, X.; Liu, Y.; Xiao, X.; Zhang, W.; Krabbendam, E.; Liu, S.; et al. Mapping global prevalence of depression among postpartum women. Transl. Psychiatry 2021, 11, 543. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, X.; Wang, S.; Wang, G. Prevalence and risk factors of postpartum depression in women: A systematic review and meta-analysis. J. Clin. Nurs. 2022, 31, 2665–2677. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tenaw, L.A.; Ngai, F.W.; Bessie, C. Effectiveness of psychosocial interventions in preventing postpartum depression among teenage mothers. Prev. Sci. 2024, 25, 1091–1103. [Google Scholar] [CrossRef] [Scilit]
- Galletta, M.A.K.; Hashimoto, A.S.; de Almeida Estrambk, G.; Verardo, I.P.S.; Cantagalli, M.H.I.; Peres, S.V.; Francisco, R.P.V. Prevalence of postpartum depression in the COVID-19 pandemic. BMC Pregnancy Childbirth 2026, 26, 157. [Google Scholar] [CrossRef] [Scilit]
- Papadopoulou, S.K.; Pavlidou, E.; Dakanalis, A.; Antasouras, G.; Vorvolakos, T.; Mentzelou, M.; Serdari, A.; Pandi, A.-L.; Spanoudaki, M.; Alexatou, O.; et al. Postpartum Depression Is Associated with Maternal Sociodemographic and Anthropometric Characteristics, Perinatal Outcomes, Breastfeeding Practices, and Mediterranean Diet Adherence. Nutrients 2023, 15, 3853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, 5th ed.; American Psychiatric Publishing: Washington, DC, USA, 2013. [Google Scholar]
- Anokye, R.; Acheampong, E.; Budu-Ainooson, A.; Obeng, E.I.; Akwasi, A.G. Prevalence of postpartum depression and interventions utilized for its management. Ann. Gen. Psychiatry 2018, 17, 18. [Google Scholar] [CrossRef] [Scilit]
- O’Hara, M.W.; McCabe, J.E. Postpartum depression: Current status and future directions. Annu. Rev. Clin. Psychol. 2013, 9, 379–407. [Google Scholar] [CrossRef] [Scilit]
- Biaggi, A.; Conroy, S.; Pawlby, S.; Pariante, C.M. Identifying the women at risk of antenatal anxiety and depression. J. Affect. Disord. 2016, 191, 62–77. [Google Scholar] [CrossRef] [Scilit]
- Stewart, D.E.; Vigod, S.N. Postpartum depression: Pathophysiology, treatment, and emerging therapeutics. Annu. Rev. Med. 2019, 70, 183–196. [Google Scholar] [CrossRef] [Scilit]
- Kendall-Tackett, K.A. Screening for perinatal depression. J. Clin. Med. 2024, 13, 6511. [Google Scholar] [CrossRef] [Scilit]
- Slomian, J.; Honvo, G.; Emonts, P.; Reginster, J.Y.; Bruyère, O. Consequences of maternal postpartum depression: A systematic review of maternal and infant outcomes. Womens Health 2019, 15, 1745506519844044. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Guide for Integration of Perinatal Mental Health in Maternal and Child Health Services; World Health Organization: Geneva, Switzerland, 2022; Available online: https://www.who.int/publications/i/item/9789240057142 (accessed on 10 January 2026).
- Amer, S.A.; Zaitoun, N.A.; Abdelsalam, H.A.; Abbas, A.; Ramadan, M.S.; Ayal, H.M.; Ba-Gais, S.E.A.; Basha, N.M.; Allahham, A.; Agyenim, E.B.; et al. Exploring predictors and prevalence of postpartum depression among mothers: Multinational study. BMC Public Health 2024, 24, 1308. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Comprehensive Mental Health Action Plan 2013–2030. 2021. Available online: https://www.who.int/publications/i/item/9789240031029 (accessed on 10 January 2026).
- European Commission. A Comprehensive Approach to Mental Health. 2023. Available online: https://health.ec.europa.eu (accessed on 10 January 2026).
- World Health Organization. Greece Mental Health Reform. 2023. Available online: https://eurohealthobservatory.who.int (accessed on 10 January 2026).
- Deniz-Garcia, A.; Fabelo, H.; Rodriguez-Almeida, A.J.; Zamora-Zamorano, G.; Castro-Fernandez, M.; Ruano, M.d.P.A.; Solvoll, T.; Granja, C.; Schopf, T.R.; Callico, G.M.; et al. Quality, usability, and effectiveness of mHealth apps. J. Med. Internet Res. 2023, 25, e44030. [Google Scholar] [CrossRef] [Scilit]
- Mustafina, S.N.; Islam, M.N.; Mahjabin, M.R.; Mannan, M.M.R.; Islam, M. Mobile application for early screening of postpartum depression. BMC Health Serv. Res. 2025, 25, 287. [Google Scholar] [CrossRef] [Scilit]
- Lewkowitz, A.; Guillen, M.; Ursino, K.; Baker, R.; Lum, L.; Battle, C.; Ware, C.; Ayala, N.; Clark, M.; Ranney, M.; et al. Optimizing a novel smartphone app to prevent postpartum depression adapted from an evidence-based cognitive behavioral therapy program: Qualitative study. JMIR Hum. Factors 2024, 11, e63143. [Google Scholar] [CrossRef] [Scilit]
- Yan, C.; Cao, R.; Hu, X.; Hu, Y.; Liu, H. A longitudinal study of a mHealth app and regional policies on the uptake of postpartum depression referral after positive screening in Shenzhen. BMC Pregnancy Childbirth 2024, 24, 536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dias, L.P.S.; Barbosa, J.L.V.; Vianna, H.D. Gamification and serious games in depression care: A systematic mapping study. Telemat. Inform. 2018, 35, 213–224. [Google Scholar] [CrossRef] [Scilit]
- Beck, K.; Beedle, M.; van Bennekum, A.; Cockburn, A.; Cunningham, W.; Fowler, M.; Grenning, J.; Highsmith, J.; Hunt, A.; Jeffries, R.; et al. Manifesto for Agile Software Development. 2001. Available online: https://agilemanifesto.org/ (accessed on 10 January 2026).
- Bensenor, I.M.; Goulart, A.C.; Thomas, G.N.; Lip, G.Y.H.; NIHR Global Health Research Group on Atrial Fibrillation Management. Patient and public involvement and engagement (PPIE): First steps in the process of engagement in research projects in Brazil. Braz. J. Med. Biol. Res. 2022, 55, e12369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cox, J.L.; Holden, J.M.; Sagovsky, R. Detection of postnatal depression: Development of the 10-item Edinburgh Postnatal Depression Scale. Br. J. Psychiatry 1987, 150, 782–786. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Parliament and Council of the European Union. Regulation (EU) 2016/679 of 27 April 2016 on the protection of natural persons with regard to the processing of personal data and on the free movement of such data (General Data Protection Regulation). Off. J. Eur. Union 2016. Available online: https://eur-lex.europa.eu/eli/reg/2016/679/oj (accessed on 10 January 2026).
- World Wide Web Consortium. Understanding Success Criterion 1.4.3: Contrast (Minimum). 2016. Available online: https://www.w3.org/TR/UNDERSTANDING-WCAG20/visual-audio-contrast-contrast.html (accessed on 10 January 2026).
- Chan, G.; Alslaity, A.; Wilson, R.; Orji, R. Feeling Moodie: Insights from a usability evaluation to improve the design of mHealth apps. Int. J. Hum.–Comput. Interact. 2023, 40, 5857–5875. [Google Scholar] [CrossRef] [Scilit]
- Lazard, A.J.; Babwah Brennen, J.; Belina, S. App designs and interactive features to increase mHealth adoption: User expectation survey and experiment. JMIR mHealth uHealth 2021, 9, e29815. [Google Scholar] [CrossRef] [Scilit]
- Pakhale, A.; Kashyap, V. User interface design recommendations for mental health mobile application design. In Design in the Era of Industry 4.0, Volume 1; Chakrabarti, A., Singh, V., Eds.; Springer: Singapore, 2023; pp. 709–721. [Google Scholar] [CrossRef] [Scilit]
- Elliot, A.J.; Maier, M.A. Color psychology: Effects of perceiving color on psychological functioning in humans. Annu. Rev. Psychol. 2014, 65, 95–120. [Google Scholar] [CrossRef] [Scilit]
- Brooke, J. SUS: A “quick and dirty” usability scale. In Usability Evaluation in Industry; Jordan, P.W., Thomas, B., McClelland, I.L., Weerdmeester, B., Eds.; Taylor & Francis: London, UK, 1996; pp. 189–194. [Google Scholar]
- Stoyanov, S.R.; Hides, L.; Kavanagh, D.J.; Wilson, H. Development and validation of the user version of the Mobile Application Rating Scale (uMARS). JMIR mHealth uHealth 2016, 4, e72. [Google Scholar] [CrossRef] [Scilit]
- Vivilaki, V.G.; Dafermos, V.; Kogevinas, M.; Bitsios, P.; Lionis, C. The Edinburgh Postnatal Depression Scale: Translation and validation for a Greek sample. BMC Public Health 2009, 9, 329. [Google Scholar] [CrossRef] [Scilit]
- Leonardou, A.; Zervas, Y.; Papageorgiou, C.; Marks, M.N.; Tsartsara, E.; Antsaklis, A.; Christodoulou, G.N. Validation of the Edinburgh Postnatal Depression Scale and prevalence of postnatal depression at two months postpartum in a sample of Greek mothers. J. Reprod. Infant Psychol. 2009, 27, 28–39. [Google Scholar] [CrossRef] [Scilit]
- Vogazianos, P.; Motrico, E.; Domínguez-Salas, S.; Christoforou, A.; Hadjigeorgiou, E. Validation of the Generalized Anxiety Disorder Screener (GAD-7) in Cypriot pregnant and postpartum women. BMC Pregnancy Childbirth 2022, 22, 841. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katsanos, C.; Tselios, N.; Xenos, M. Perceived usability evaluation of learning management systems: A first step towards standardization of the System Usability Scale in Greek. In Proceedings of the 16th Panhellenic Conference on Informatics; IEEE: New York, NY, USA, 2012; pp. 302–307. [Google Scholar]
- Spitzer, R.L.; Kroenke, K.; Williams, J.B.W.; Löwe, B. A brief measure for assessing generalized anxiety disorder: The GAD-7. Arch. Intern. Med. 2006, 166, 1092–1097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chasiotis, G.; Stoyanov, S.R.; Karatzas, A.; Gravas, S. Greek validation of the user version of the Mobile Application Rating Scale (uMARS). J. Int. Med. Res. 2023, 51, 03000605231161213. [Google Scholar] [CrossRef] [Scilit]
- Ritchie, J.; Spencer, L. Qualitative data analysis for applied policy research. In Analyzing Qualitative Data; Bryman, A., Burgess, R.G., Eds.; Routledge: London, UK, 1994; pp. 173–194. [Google Scholar]
- Torous, J.; Nicholas, J.; Larsen, M.E.; Firth, J.; Christensen, H. Clinical review of user engagement with mental health smartphone apps: Evidence, theory and improvements. Evid. Based Ment. Health 2018, 21, 116–119. [Google Scholar] [CrossRef] [Scilit]
- Baumel, A.; Muench, F.; Edan, S.; Kane, J.M. Objective user engagement with mental health apps: Systematic search and panel-based usage analysis. J. Med. Internet Res. 2019, 21, e14567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, F.D. Perceived usefulness, perceived ease of use, and user acceptance of information technology. MIS Q. 1989, 13, 319–340. [Google Scholar] [CrossRef] [Scilit]
- Loughnan, S.A.; Butler, C.; Sie, A.A.; Grierson, A.B.; Chen, A.Z.; Hobbs, M.J.; Joubert, A.E.; Haskelberg, H.; Mahoney, A.; Holt, C.; et al. A randomised controlled trial of “MUMentum postnatal”: Internet-delivered cognitive behavioural therapy for anxiety and depression in postpartum women. Behav. Res. Ther. 2019, 116, 94–103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huckvale, K.; Torous, J.; Larsen, M.E. Assessment of the data sharing and privacy practices of smartphone apps for depression and smoking cessation. JAMA Netw. Open 2019, 2, e192542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Loughlin, K.; Neary, M.; Adkins, E.C.; Schueller, S.M. Reviewing the data security and privacy policies of mobile apps for depression. Internet Interv. 2019, 15, 110–115. [Google Scholar] [CrossRef] [Scilit]
- Arbelaez, A.; Climent, L. Iterative local search for preserving data privacy. Appl. Intell. 2025, 55, 189. [Google Scholar] [CrossRef] [Scilit]
- Schmettow, M. Sample size in usability studies. Commun. ACM 2012, 55, 64–70. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.