


Abstract
Objective: This study provides the first systematic synthesis of the burden of Group B Streptococcus (GBS) colonization and invasive disease in Nigeria, with emphasis on prevalence, serotypes, and sequence types (STs). Method: This systematic review and meta-analysis were conducted in accordance with the PRISMA guidelines and was registered on PROSPERO (CRD420251155310). Searches were conducted across multiple databases, including Scopus, ScienceDirect, Web of Science, PubMed, Dimensions, and African Journals Online, as well as in Google Scholar and Google to identify relevant articles. In total, 426 records were retrieved, of which 43 studies met the inclusion criteria. A random-effects model was applied to estimate the pooled prevalence. Result: The pooled prevalence of GBS colonization in Nigeria was 12.0% (95% CI: 9.0–15.0%). Higher colonization rates were observed in Southern Nigeria (13.0%) than in Northern Nigeria (9.0%). The neonatal colonization rate was 16.0%. Colonization rates were 13.0% in pregnant women and 8.0% in non-pregnant individuals. Human immunodeficiency virus status showed no significant association with GBS colonization among pregnant women (OR = 1.47, p = 0.17). Invasive GBS disease was uncommon (3.0%) and occurred only in neonates. Across included studies, serotypes V and II were the most frequently reported, with ST19, ST182, and ST28 being the predominant STs. Conclusions: GBS colonization is common in Nigeria, with marked regional variation and heightened neonatal vulnerability to invasive GBS infections. Notably, nineteen states lacked surveillance data, highlighting substantial gaps in national monitoring. These findings highlight the importance of strengthening prevention strategies, expanding surveillance coverage, and implementing maternal screening and immunization programs to mitigate the burden of GBS.
1. Introduction
Streptococcus agalactiae (Group B Streptococcus; GBS) is a Gram-positive bacterium that occupies a unique niche at the interface of commensalism and invasive disease [1]. It commonly colonizes the gastrointestinal and genitourinary tracts of humans without symptoms, yet under certain circumstances, it can cause severe infections [1,2]. The clinical impact of GBS varies across populations, ranging from neonatal sepsis, pneumonia, and meningitis to maternal puerperal infections, chorioamnionitis, and invasive disease in non-pregnant adults, particularly the elderly and immunocompromised [2,3,4,5,6]. A 2020 global estimate attributed nearly 20 million maternal colonizations to GBS, resulting in approximately 394,000 infant infections, 58,000–92,000 neonatal deaths, 37,000 cases of long-term disability, more than 40,000 maternal infections, and 46,000 stillbirths [2].
GBS is heterogeneous. Isolates are classified into ten capsular polysaccharide serotypes (Ia–IX) [7,8,9] and by sequence types (STs) using multilocus sequence typing (MLST) [9,10,11]. Serotype and lineage distributions vary by region, host population, and clinical syndrome [3,7,9,12]. Globally, serotypes Ia, III, and V are predominant, associated with ST23, ST17, and ST1, respectively [6,8,11]. These differences are critical as they influence vaccine design, disease risk, and interpretation of surveillance data [11].
Maternal colonization prevalence also varies widely [13]. Multicountry studies report rates of 10–30%, though with heterogeneity by country and sampling methods [7,14,15,16]. In sub-Saharan Africa, prevalence estimates remain fragmentary due to limited surveillance and laboratory capacity [8]. Local prevalence data are essential since maternal colonization is the primary upstream risk factor for neonatal exposure and early-onset disease (EOD), making colonization, serotype distribution, and ST data vital for informing intrapartum antibiotic prophylaxis (IAP) policies and maternal vaccine strategies [13,17,18].
Nigeria, home to over 221 million people and one of the world’s highest birth rates, records 34.3 neonatal deaths per 1000 live births, ranking fifth globally [19]. This population growth significantly impacts public health [20]. Despite this, GBS data remain fragmented, with variable colonization and invasive estimates and limited serotype/ST characterization [12,18,21,22,23,24]. Weak surveillance systems, uneven laboratory capacity, and limited intrapartum screening further constrain detection [7,12,14,15,16]. This study represents the first systematic review and meta-analysis of the burden of GBS in Nigeria. We aimed to synthesize evidence on colonization and invasive disease, determine pooled prevalence across populations, serotype and ST distributions, and identify knowledge gaps to inform prevention strategies.
2. Methods
2.1. Protocol Registration and Reporting Standards
The review protocol was registered with the International Prospective Register of Systematic Reviews (PROSPERO) on 30 September 2025 under the registration number CRD420251155310. This systematic review and meta-analysis were conducted in accordance with the PRISMA 2020 guidelines (Supplementary Table S1), focusing on the prevalence of GBS colonization and invasive disease among neonates, pregnant women, and non-pregnant populations in Nigeria [25].
2.2. Eligibility Criteria
Original studies that described the study population and design and reported the prevalence (or sufficient data to calculate prevalence) of GBS colonization or invasive disease among neonates, pregnant women or non-pregnant populations in Nigeria and/or study which conducted serotyping or MLST for GBS isolates were includes while exclusion criteria include studies of GBS in other hosts, human GBS studies with unclear results, reviews, letters, commentaries, editorials, and studies that did not provide proportion/prevalence data among human participants are excluded.
2.3. Information Sources
We systematically searched literature published between 1 January 1984, and 31 December 2024, in Scopus, ScienceDirect, Web of Science, PubMed, Dimensions, Africa Journals Online, Google Scholar, and Google.
2.4. Search Strategy
Search terms combined “Streptococcus agalactiae” OR “Group B Streptococcus” OR “Group B streptococci” OR “Group B streptococcal” AND “Nigeria”. Detailed search strings for each database are provided in Supplementary Table S2.
2.5. Selection Process
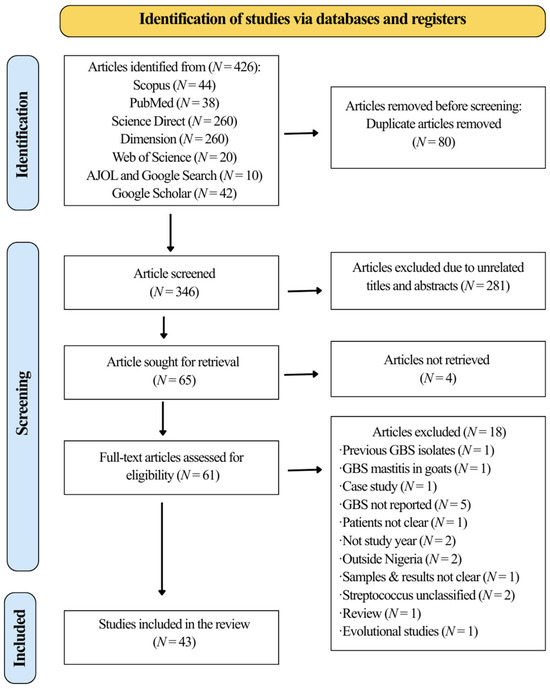
All 426 records were imported into Rayyan software, and 80 duplicates were removed using a combination of exact matching criteria (title and author) and fuzzy logic [26]. After deduplication, 346 unique records remained. Two reviewers (AA and BHG) independently screened the titles, abstracts, and full texts of the articles. Of these, 281 articles were excluded at the title and abstract screening stage because they were not related to GBS in Nigeria. Sixty-five articles were sought for retrieval, of which four could not be retrieved. The remaining 61 articles underwent full-text screening, resulting in the exclusion of 19 studies. These excluded studies included review articles, letter to editors, commentaries, studies conducted in other countries, studies involving non-classified Streptococcus species, GBS studies in animals, non-GBS studies, studies with unclear sample sizes and results, and studies conducted outside the period 1984 to 2024 (Supplementary Table S3). Finally, 42 articles met the inclusion criteria and were included in the study. Any disagreements were resolved through discussion or, when necessary, by consultation with a third reviewer (VAA). The PRISMA 2020 flow diagram (Figure 1) illustrates the study selection process and the reasons for exclusion at the full-text stage.
Figure 1.
The study flow diagram demonstrates the study selection process.
2.6. Data Collection Process
Data were extracted into an Excel spreadsheet by two independent reviewers (AA and VAA) and cross-checked; disagreements were resolved by consensus. Extracted items included: first author (or first and second author where two authors were listed), publication year, state and geopolitical zone, study population (neonates, pregnant women, non-pregnant), sample size, number of GBS identified, specimen type, serotype distribution, and ST data (if performed) (Table 1).
2.7. Study Risk of Bias Assessment
AA and VAA independently assessed methodological quality using an adapted Joanna Briggs Institute (JBI) critical appraisal checklist [27]. A composite quality score (0–10) was assigned to each study using an adapted JBI checklist for prevalence studies. We prespecified ≥6/10 as moderate to high quality to reflect adequate sampling, an appropriate case definition, valid measurement, and acceptable response rates. Studies with scores < 6 were classified as lower quality (Supplementary Table S4). BHG adjudicated any disagreements.
2.8. Synthesis Methods
The data were synthesized using an online meta-analysis software available at https://metaanalysisonline.com (4 October 2025) [28]. In view of the substantial heterogeneity across studies, pooled prevalence estimates of GBS colonization and invasive infection in Nigeria were calculated using a random-effects model with 95% confidence intervals as well as meta-regression. The analyses were stratified by geographical region and by population groups, including neonates, pregnant women, and non-pregnant women. Serotype and ST distributions were summarized descriptively. We calculated pooled odds ratios and 95% confidence intervals. Results will be presented as tables and graphical displays, including forest plots and a map.
Table 1.
Summary of the characteristics of the included studies.
2.9. Reporting Bias Assessment
Publication bias was assessed visually using funnel plots, tables, and formally with trim-and-fill analysis and Egger’s regression tests; a p-value ≤ 0.05 was considered evidence of small-study effects.
3. Results
3.1. Study Selection and Study Characteristics
3.2. Prevalence of Group B Streptococcus Colonization in Nigeria
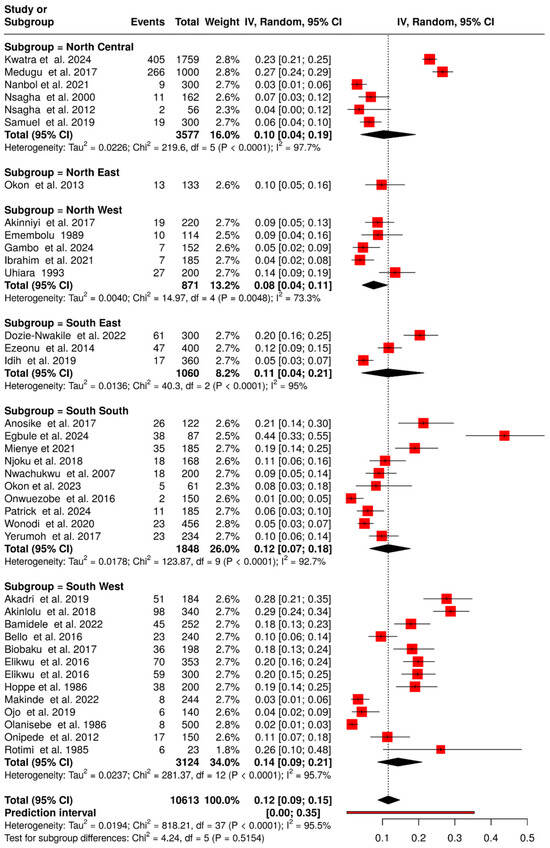
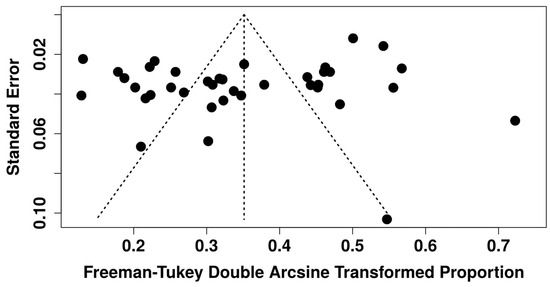
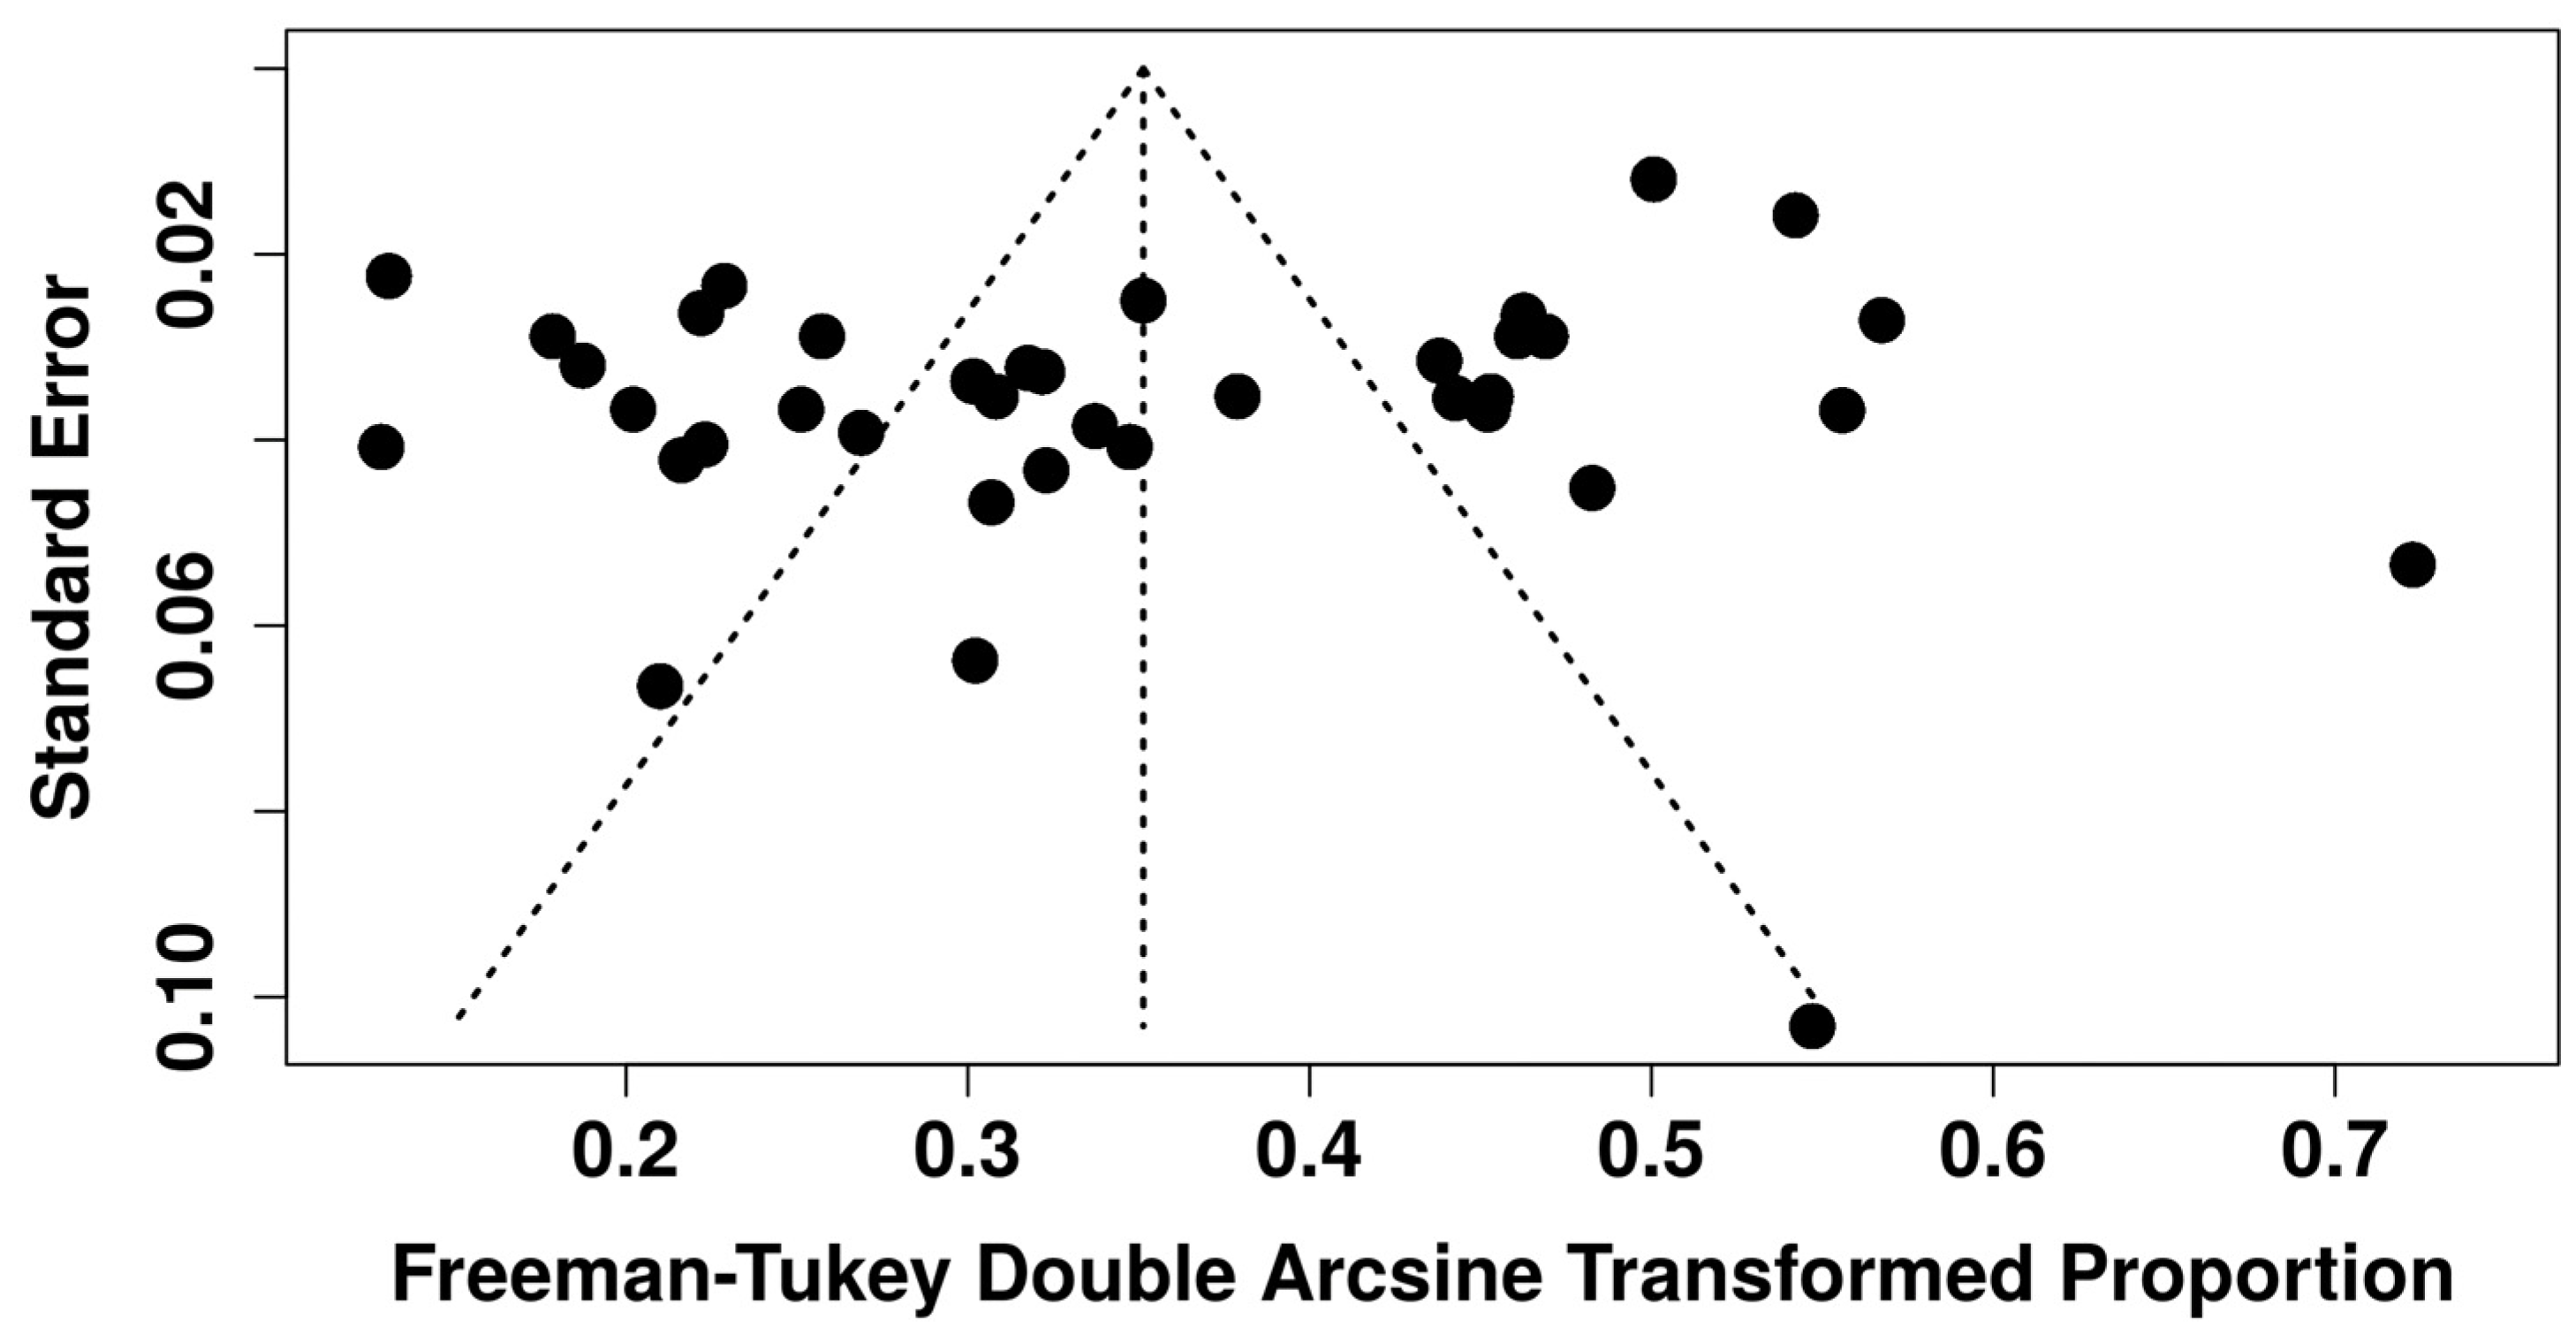
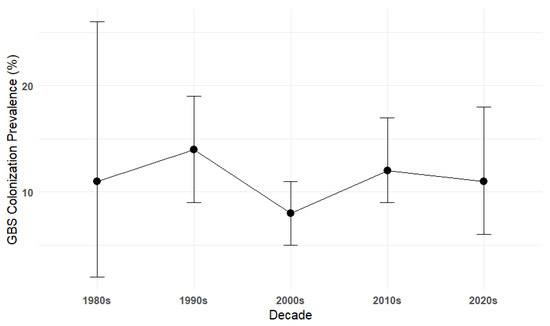
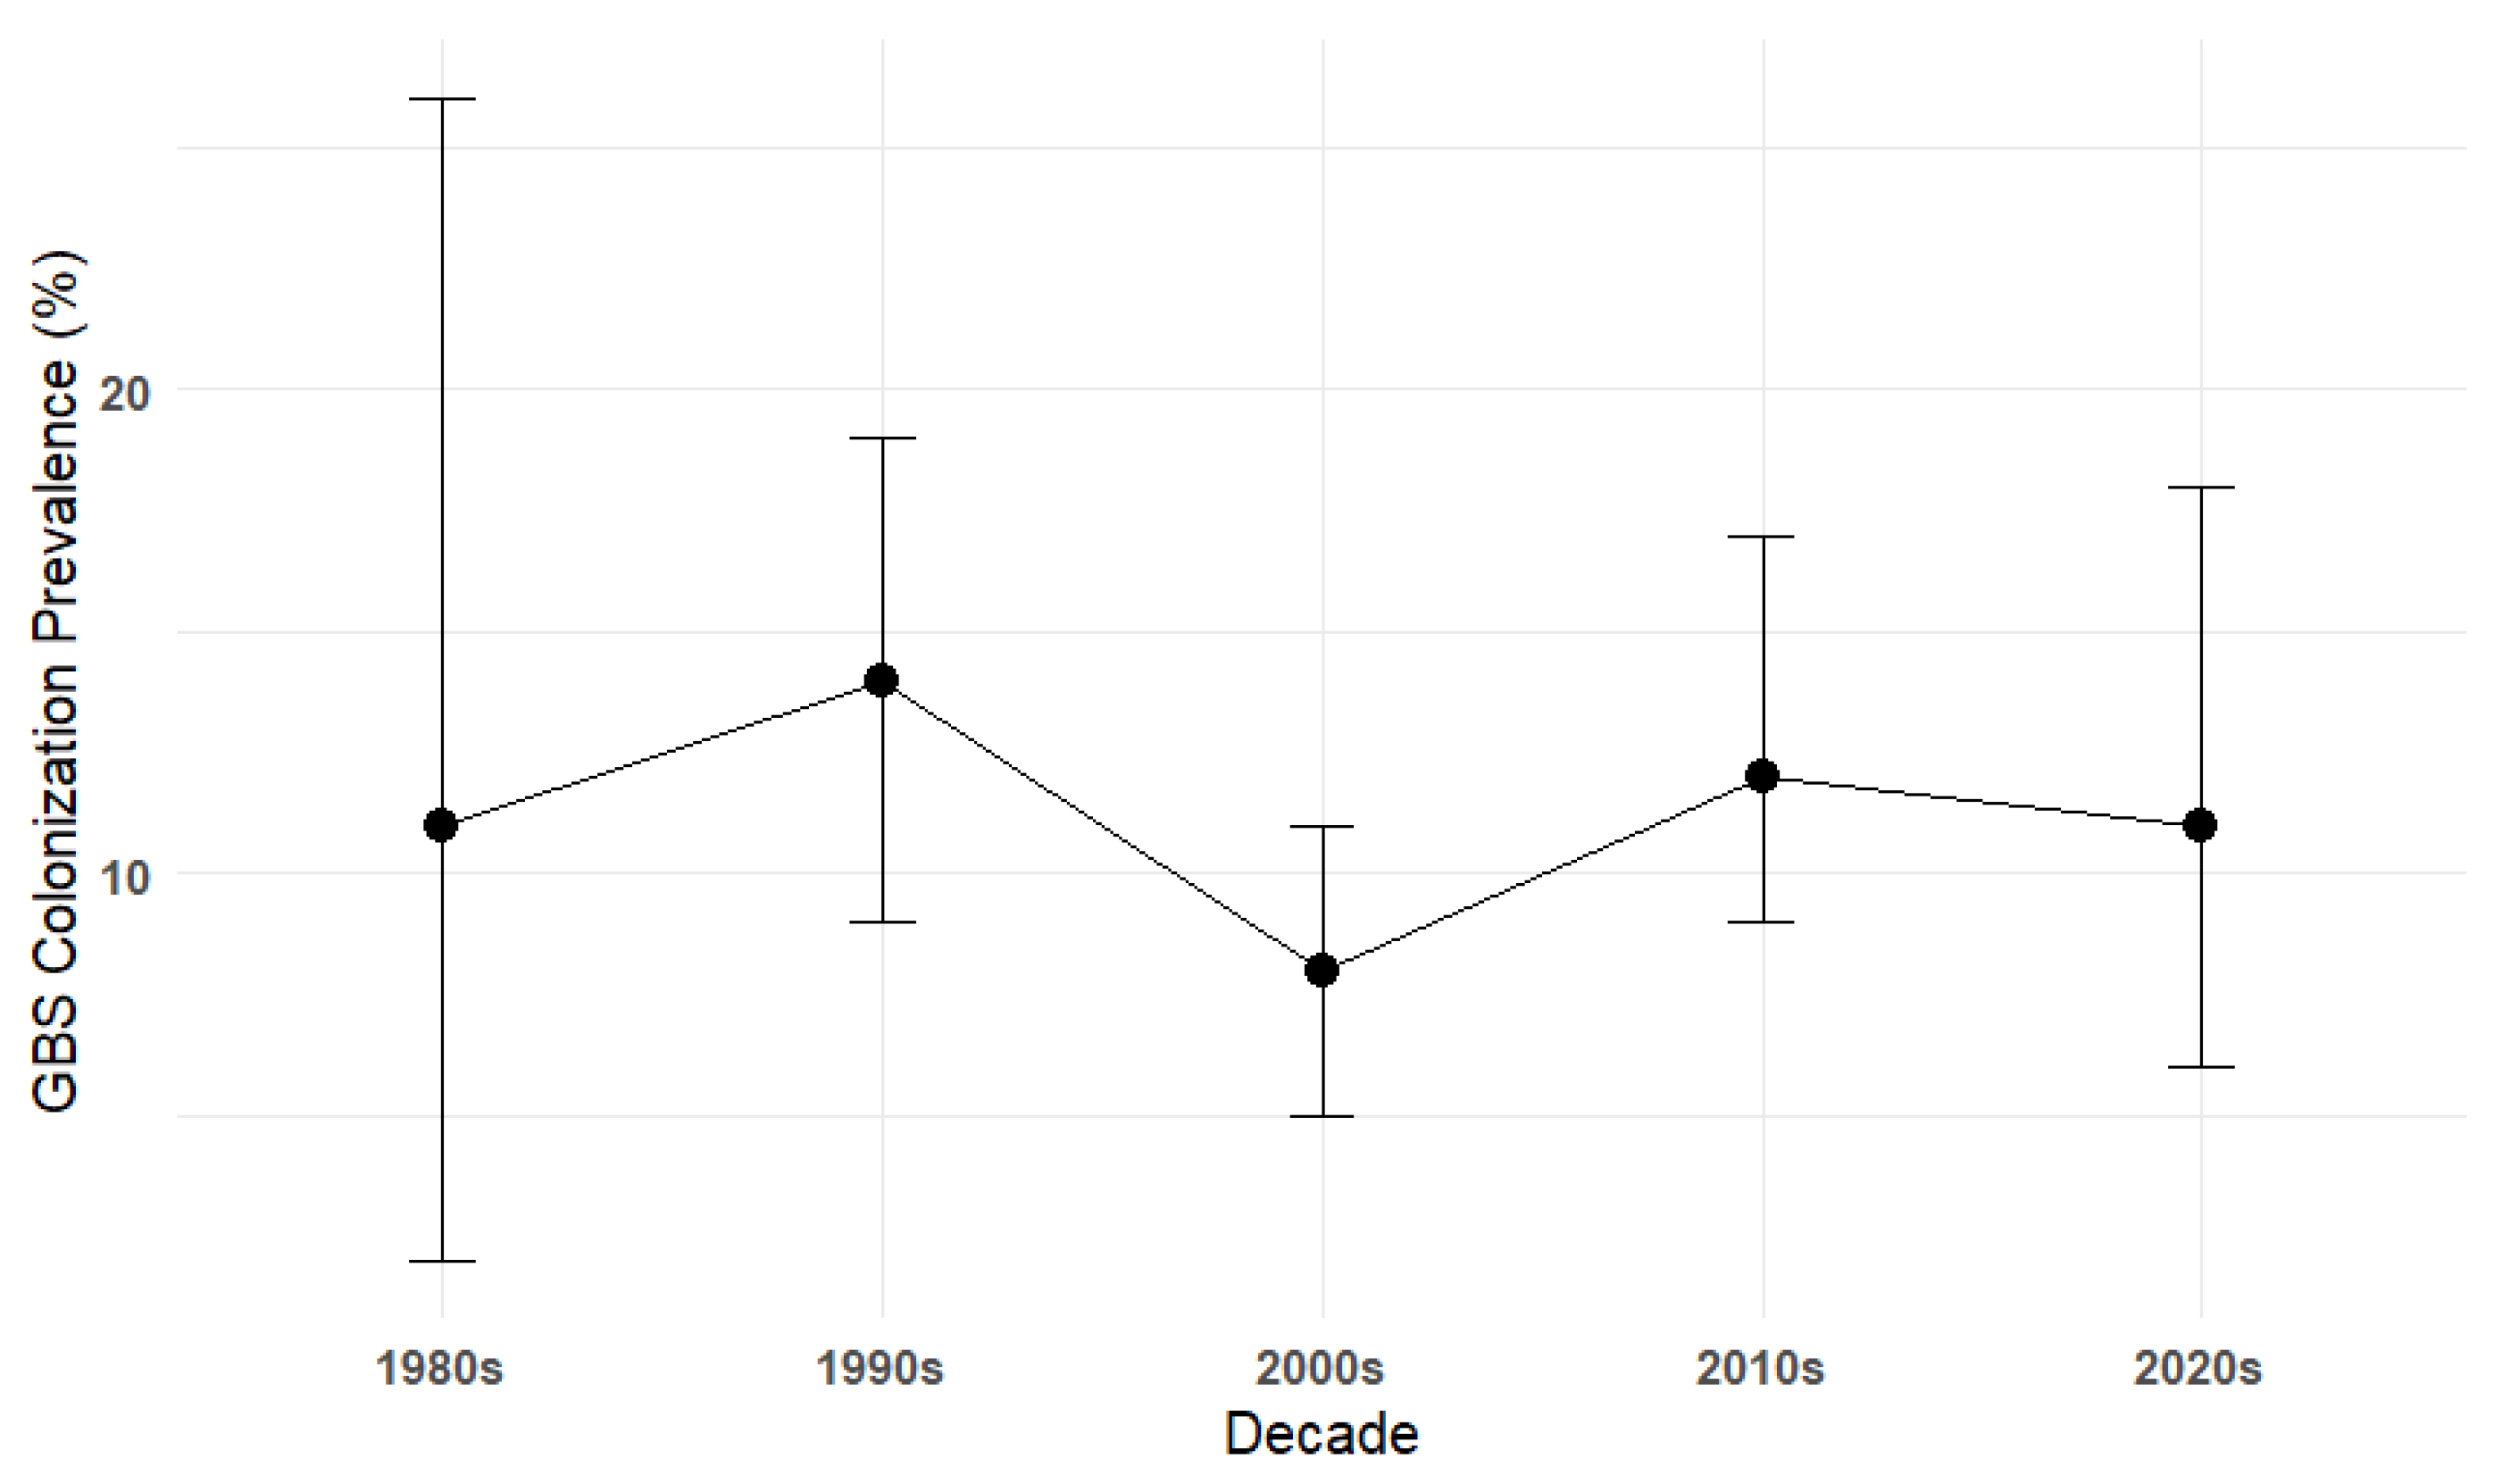
Of the 43 included studies, 38 reported GBS colonization, resulting in 1584 GBS-positive cases among 10,613 individuals, which translates to an overall prevalence of 12.0% (95% CI: 9.0–15.0%) (Figure 2). Evidence of publication bias was suggested by funnel plot asymmetry and Egger’s test (intercept: −4.22, p = 0.034) (Figure 3, Supplementary Table S5). To further assess the impact of potential publication bias, a trim-and-fill analysis was conducted under a random-effects model. No potentially missing studies were imputed (k0 = 0), and the adjusted pooled prevalence remained unchanged, indicating that the overall estimate was robust to the influence of publication bias. In addition, sensitivity analysis excluding two large studies [12,17] and one small study [60] yielded a prevalence of 11.0% (95% CI: 8.0–14.0%), while heterogeneity remained high (I2 = 93.6%) and no evidence of publication bias (Egger’s intercept: 2.47, p = 0.401), confirming the robustness of estimates. To explore sources of heterogeneity, a meta-regression was conducted using study years (in decades) as a moderator, with the 1980s as the reference category. The baseline prevalence in the 1980s was 11.0% (95% CI: 2.0–22.0%). No statistically significant differences were observed across subsequent decades (1990s–2020s), as reflected by overlapping confidence intervals, indicating the absence of a clear temporal trend (Figure 4). Substantial residual heterogeneity remained after adjustment.
Figure 2.
Forest plot of GBS colonization prevalence in Nigeria and geopolitical zones (1984–2024). The pooled prevalence was estimated using random-effects models [12,17,18,21,22,23,24,29,30,31,32,33,35,36,37,38,40,41,42,43,44,45,46,47,48,49,50,53,54,55,56,57,59,60,61,62,63,64]. Each black horizontal line represents a study’s 95% confidence interval, with red squares indicating point estimates and weights. Black diamonds denote comparisons, while dotted or dashed lines show subgroup analyses. The red horizontal line represents the prediction interval.
Figure 3.
The funnel plot of studies conducted on Group B Streptococcus colonization rates in Nigeria between 1984 and 2024 demonstrates an asymmetrical distribution.
Figure 4.
Colonization prevalence of Group B Streptococcus by decade with 95% confidence intervals. Black circles show the estimated GBS prevalence per decade, with vertical black lines represent 95% confidence intervals.
Prevalence was higher in the South (13.0% [95% CI: 9.0–17.0%]) than in the North (9.0% [95% CI: 5.0–15.0%]). Across geopolitical zones, the South West recorded the highest prevalence (14.0% [95% CI: 9.0–21.0%]; 13 studies [18,21,22,29,31,32,37,38,43,50,55,56,60]), followed by the South South (12.0% [95% CI: 7.0–18.0%]; 10 studies [23,33,36,47,49,54,57,59,63,64]). The South East showed 11.0% (95% CI: 4.0–21.0%; 3 studies [33,45,63]), the North Central 10.0% (95% CI: 4.0–19.0%; 6 studies [12,17,24,46,48,61], and the North East 10.0% (95% CI: 5.0–16.0%; 1 study [53]). The lowest prevalence was in the North West (8.0% [95% CI: 4.0–11.0%]; 5 studies [30,40,42,44,62]).
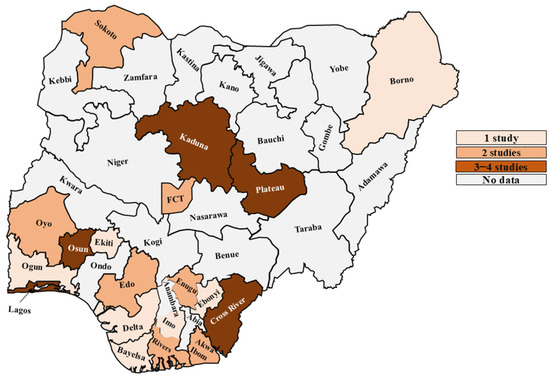
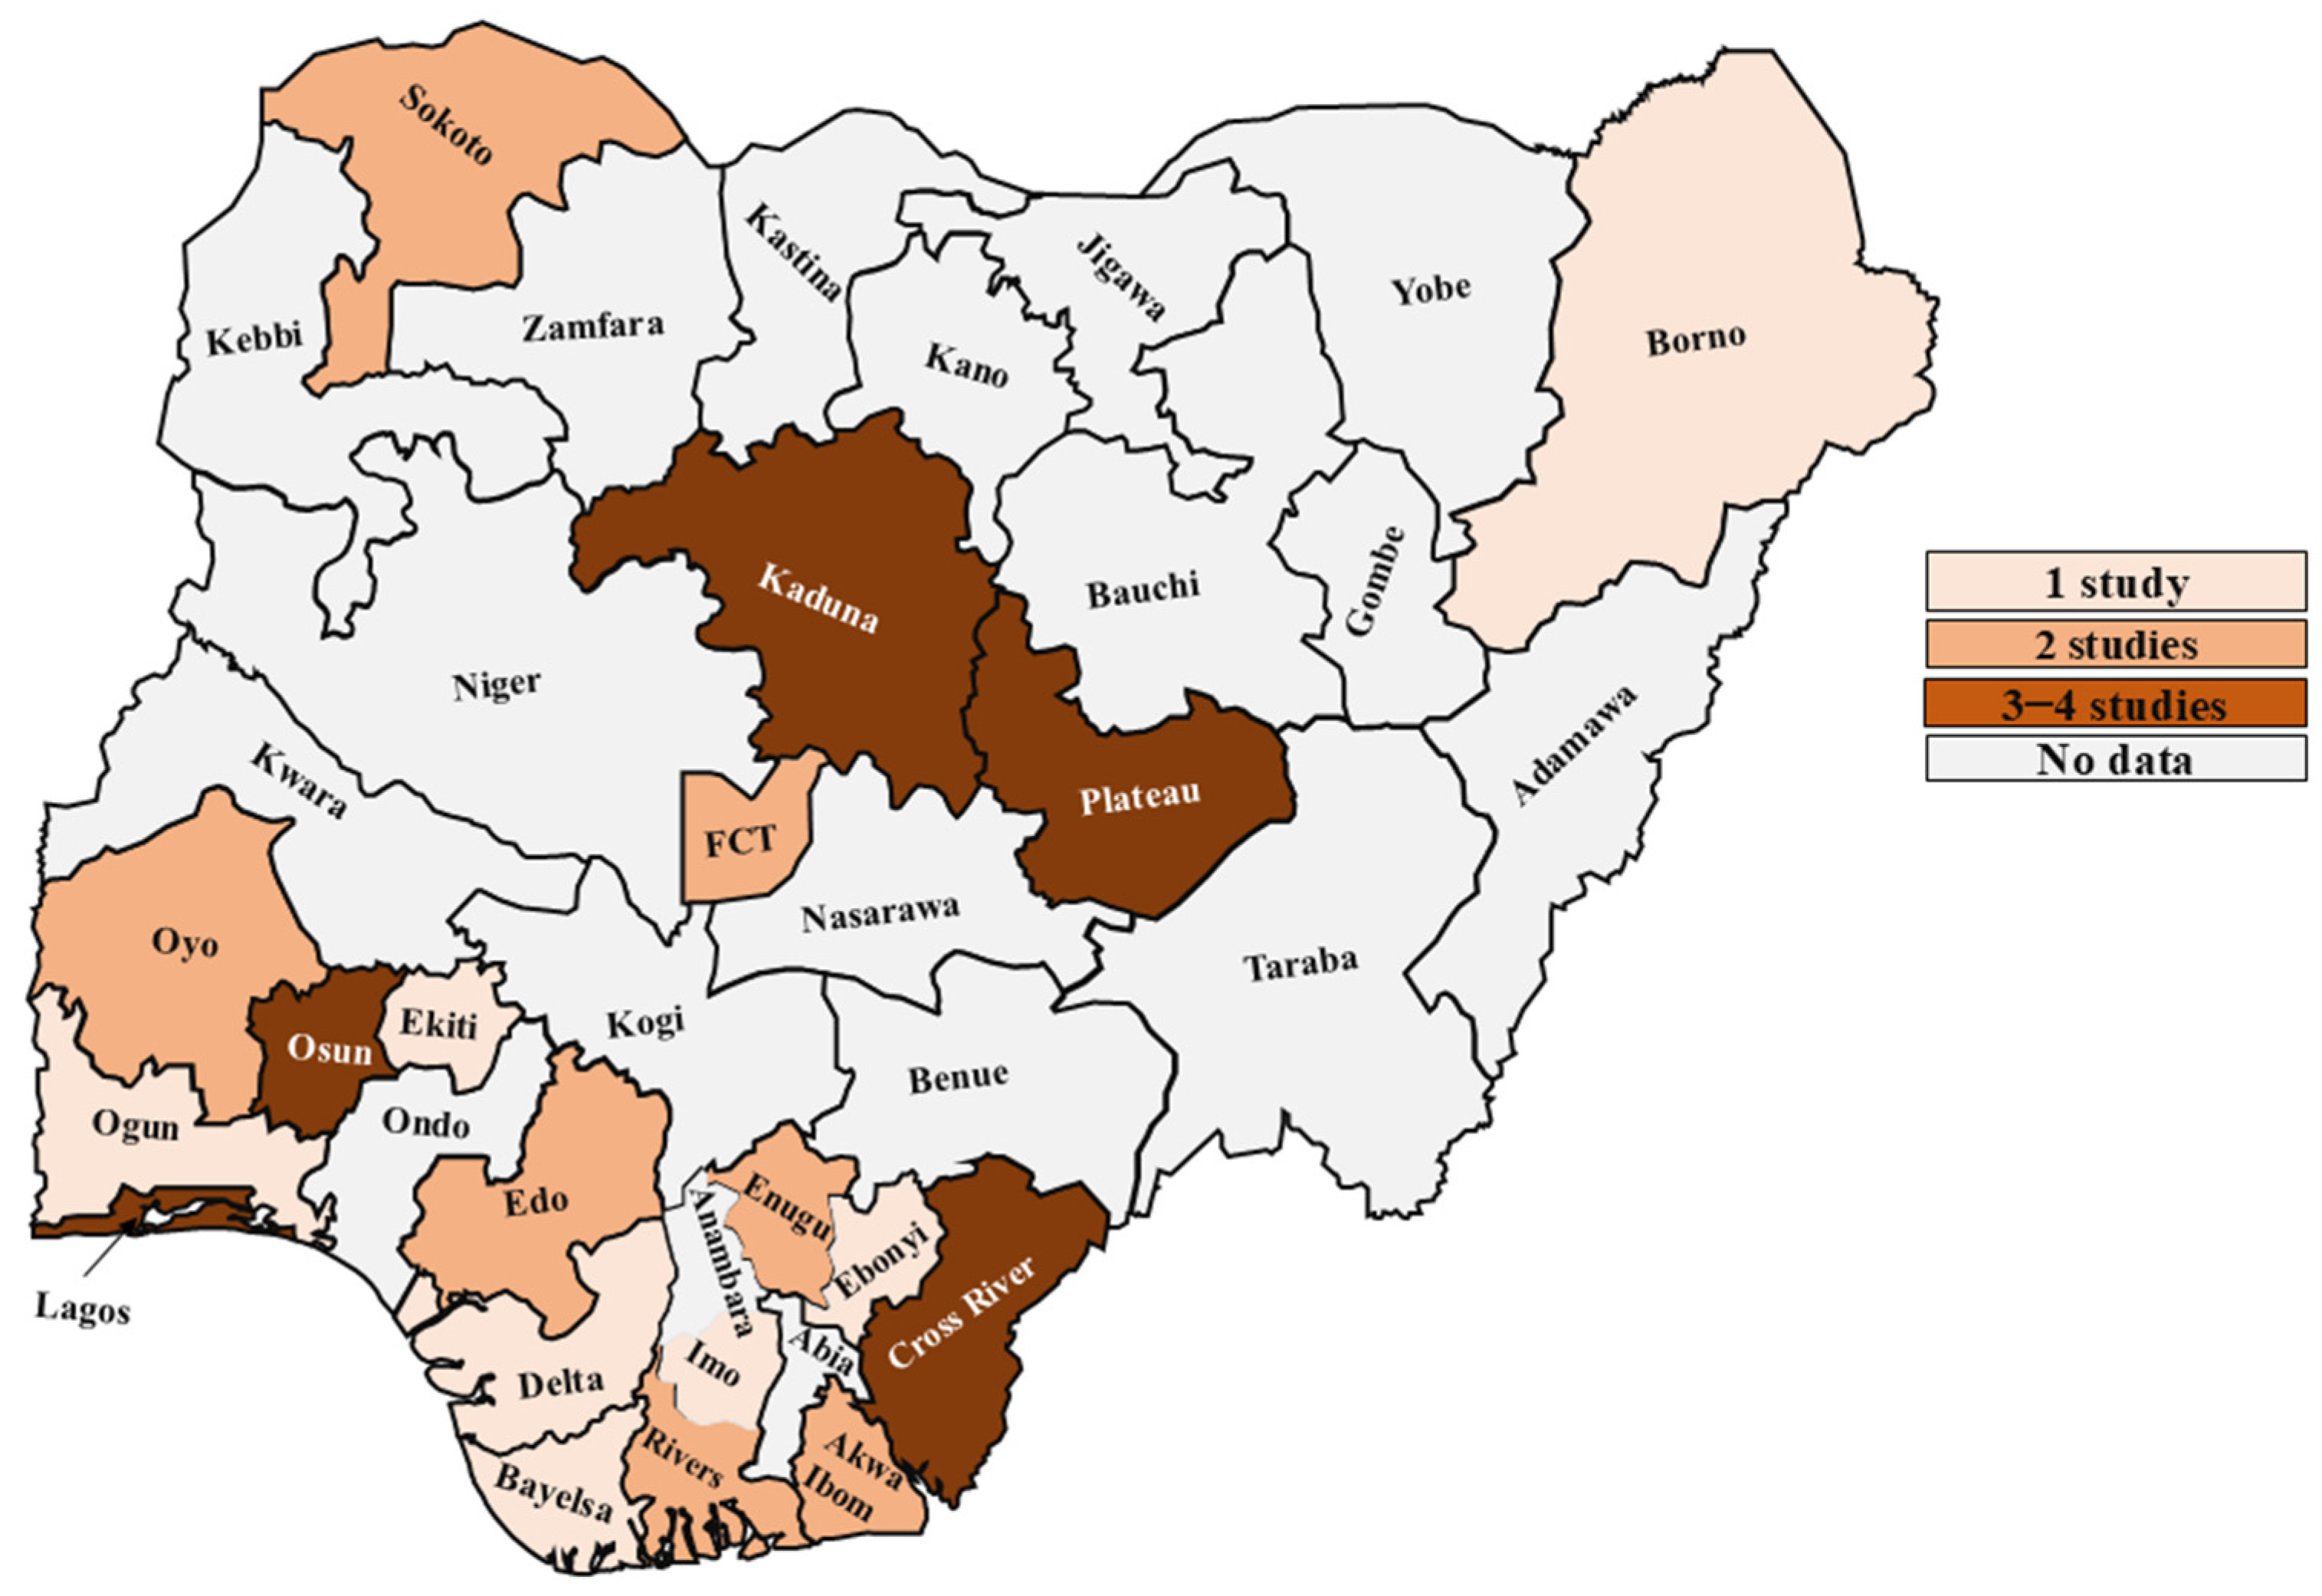
No data were available for 18 states, including Ondo, Abia, Anambra, Ebonyi, Benue, Kogi, Kwara, Nasarawa, Adamawa, Bauchi, Gombe, Taraba, Yobe, Jigawa, Kano, Katsina, Kebbi, and Zamfara (Figure 5).
Figure 5.
Distribution of studies across Nigerian states from 1984 to 2024, highlighting the range of data available per state.
3.3. Prevalence of Group B Streptococcus Colonization in the Neonate
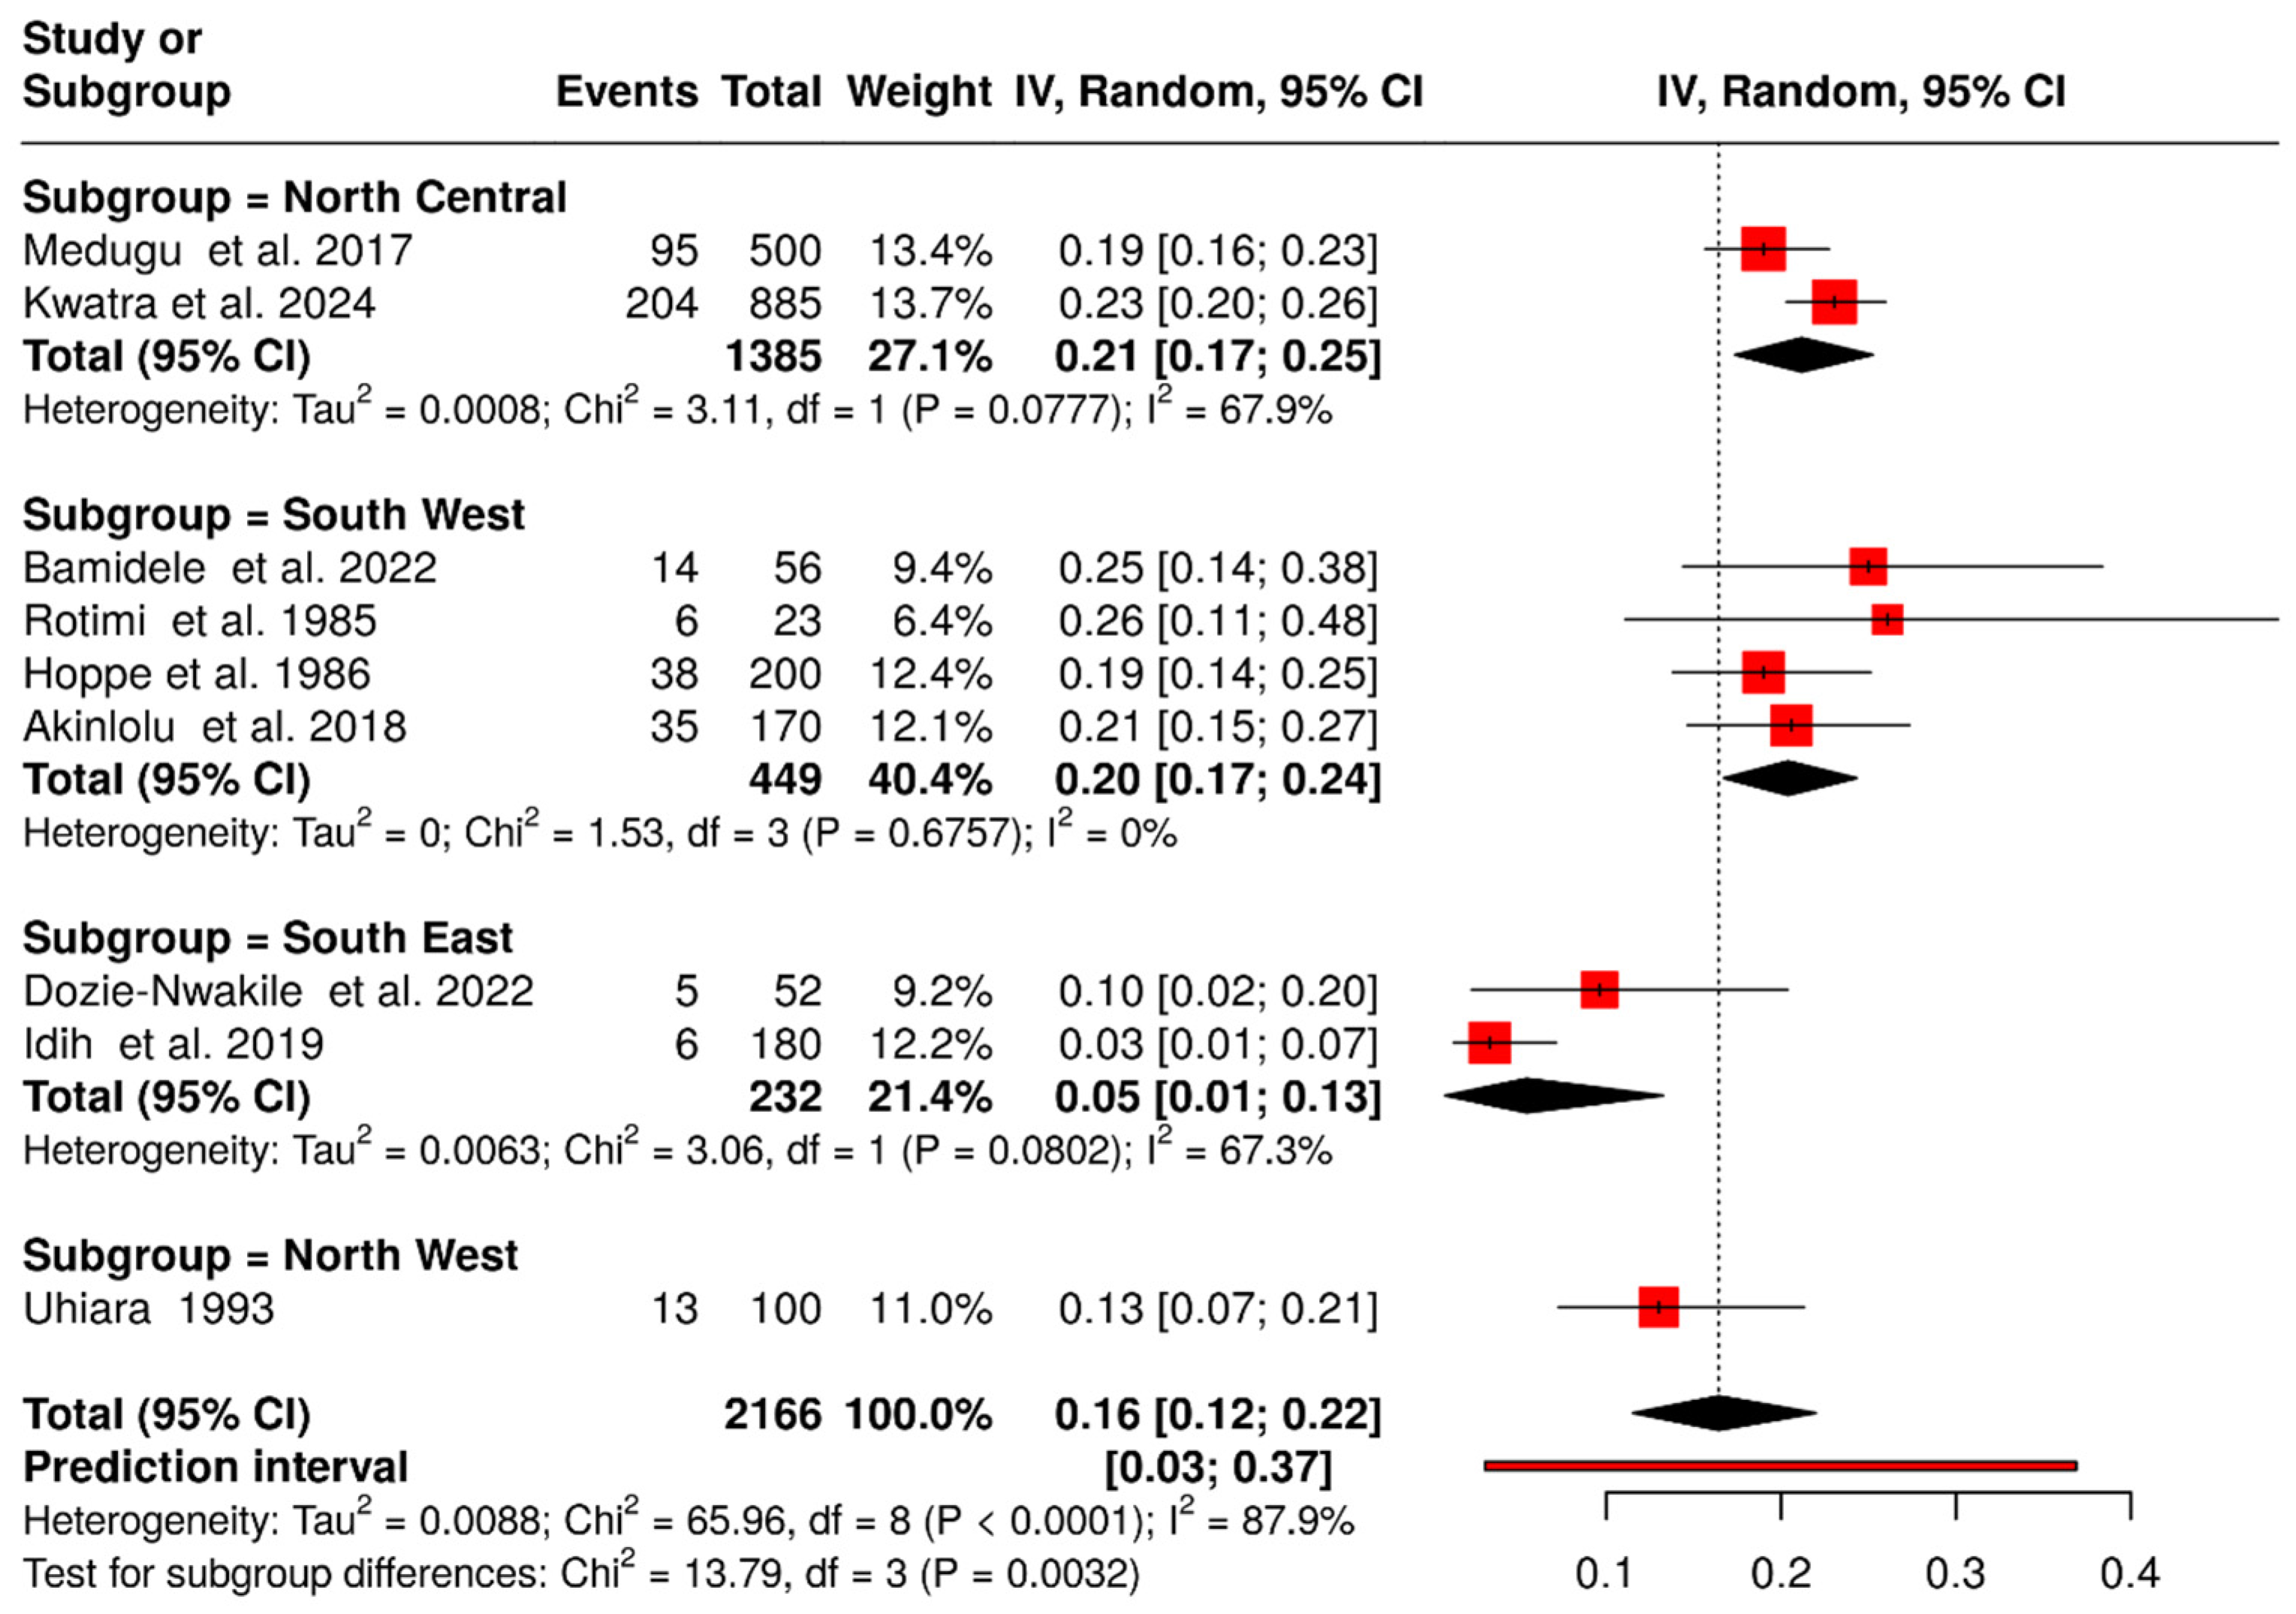
Nine of the 38 included studies reported on GBS colonization in neonates, involving a total of 2166 neonates across nine states of Nigeria [12,17,29,31,35,43,45,60,62]. Among these, 416 cases of GBS were identified, yielding a pooled prevalence of 16.0% (95% CI: 12.0–22.0%) (Figure 6).
Figure 6.
Forest plot of Neonatal GBS colonization prevalence in Nigeria and per geographical zones (1984–2024). The pooled prevalence was estimated using random-effects models [12,17,29,31,35,43,45,60,62]. Each black horizontal line represents a study’s 95% confidence interval, with red squares indicating point estimates and weights. Black diamonds denote comparisons, while dotted or dashed lines show subgroup analyses. The red horizontal line represents the prediction interval.
Regionally, the northern part of the country reported the highest number of neonatal GBS cases, with 312 cases out of 1485 neonates, corresponding to a prevalence of 19.0% (95% CI: 15.0–24.0%) [12,17,62]. In contrast, the southern region reported 104 cases out of 681 neonates, with a prevalence of 16.0% (95% CI: 8.0–25.0%) [18,29,31,43,45].
3.4. Prevalence of Group B Streptococcus Colonization in Pregnant Women
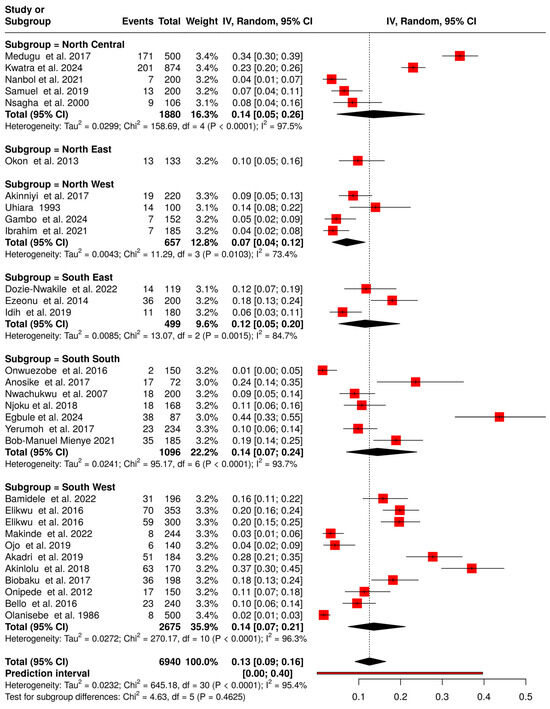
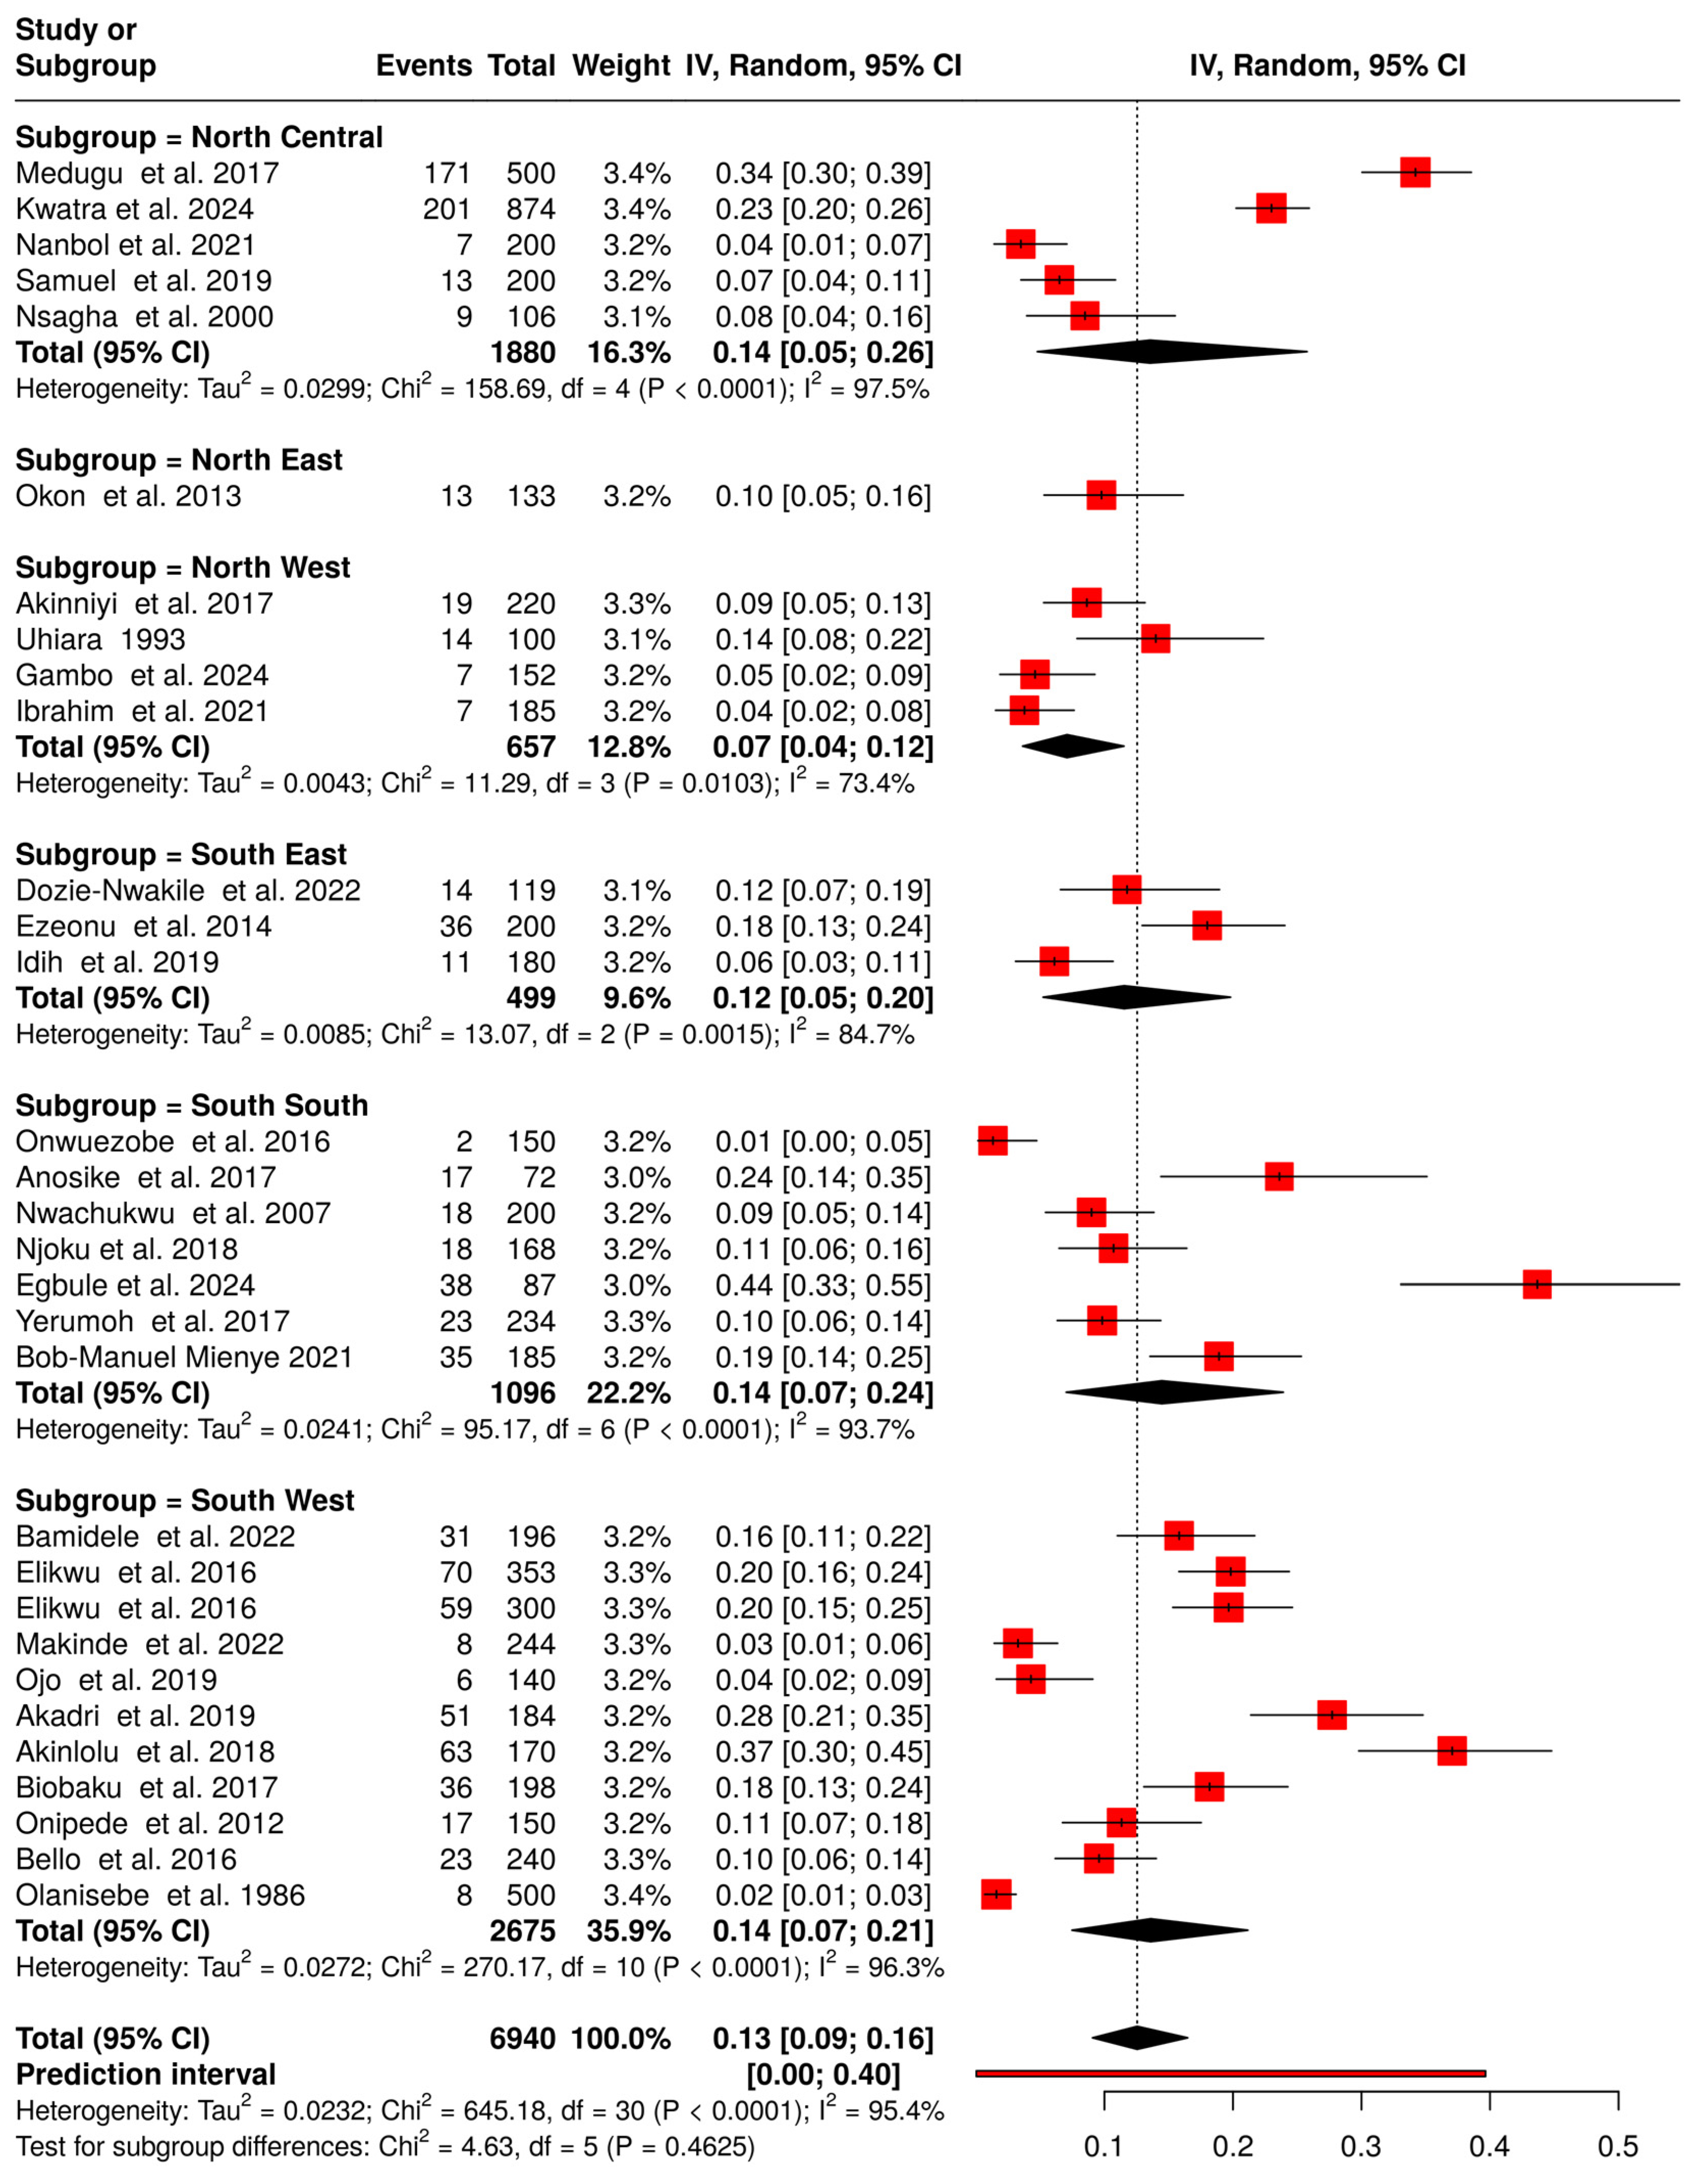
Thirty-one of the 38 included articles reported maternal colonization in Nigeria, involving a total of 6,940 women, of whom 1,045 were colonized, resulting in an overall prevalence of 13% (95% CI: 9.0–16.0%) (Figure 7). Prevalence was higher in the southern region of Nigeria (14.0% [95% CI: 9.0–18.0%]) compared to the northern region (11.0% [95% CI: 5.0–18.0%]).
Figure 7.
Forest plot of Maternal GBS colonization prevalence in Nigeria and geopolitical zones (1984–2024). The pooled prevalence was estimated using random-effects models [12,17,18,21,22,23,29,30,31,32,33,35,36,37,38,41,42,44,45,46,47,48,49,50,53,55,56,57,61,62,64]. Each black horizontal line represents a study’s 95% confidence interval, with red squares indicating point estimates and weights. Black diamonds denote comparisons, while dotted or dashed lines show subgroup analyses. The red horizontal line represents the prediction interval.
Regional analysis showed that prevalence was highest in the North Central (14.0% [95% CI: 5.0–26.0%]; 5 studies [12,17,46,48,61] and lowest in the North West (7.0% [95% CI: 4.0–12.0%]; 4 studies [30,42,44,62]). The North East (10.0% [95% CI: 5.0–16.0%]; 1 study [53]) had intermediate prevalence. In the southern regions, South South (14.0% [95% CI: 7.0–24.0%]; 7 studies [23,33,36,47,49,57,64]), South East (12.0% [95% CI: 5.0–20.0%]; 3 studies [35,41,45]), and South West (14.0% [95% CI: 7.0–21.0%]; 11 studies showed similar prevalence across regions [18,21,22,29,31,32,37,38,50,55,56].
3.5. Prevalence of Maternal Group B Streptococcus Colonization in HIV Pregnant Women
Three studies assessed GBS colonization among HIV-positive pregnant women [18,32,47]. The individual studies reported prevalence estimates of 3.0% [18], 15.0% [47], and 19.0% [32], respectively, reflecting variability across study populations and settings. When the data were pooled, the overall prevalence of GBS colonization in this subgroup was estimated at 11.0% (95% CI: 3.0–25.0%), suggesting that HIV-positive women may have a moderate burden of GBS colonization. However, the wide confidence interval indicates uncertainty in the estimate and highlights the need for further studies with larger sample sizes to provide more precise prevalence data.
3.6. Impact of HIV on Maternal Group B Streptococcus Colonization
Three studies assessed maternal GBS colonization in HIV-positive and HIV-negative pregnant women [18,32,47]. The odds ratios from individual studies ranged from 1.00 to 2.89. A pooled Mantel–Haenszel meta-analysis showed no statistically significant association between HIV status and GBS colonization (OR = 1.47, 95% CI: 0.85–2.54, p = 0.17) (Table S5).
3.7. Prevalence of Group B Streptococcus Colonization in Non-Pregnant Individuals
In addition to neonates and pregnant women, 11 studies reported GBS colonization among non-pregnant women, men, and school children [23,24,35,40,41,46,48,54,59,61,63], with a pooled prevalence of 8.0% (95% CI: 4.0–13.0%) (Figure 8). Of these, five studies were conducted in the northern region, involving 426 individuals, among whom 22 GBS isolates were identified, corresponding to a prevalence of 5.0% (95% CI: 3.0–8.0%) [24,40,46,48,61]. In contrast, studies from the southern region reported 103 GBS isolates out of 1081 individuals, yielding a prevalence of 11.0% (95% CI: 4.0–20.0%) [23,35,41,54,59,63].
Figure 8.
Forest plot of prevalence of colonization of GBS in non-pregnant, non-neonate in Nigeria and per geographical zones (1984–2024). The pooled prevalence was estimated using random-effects models [23,24,35,40,41,46,48,53,59,61,63]. Each black horizontal line represents a study’s 95% confidence interval, with red squares indicating point estimates and weights. Black diamonds denote comparisons, while dotted or dashed lines show subgroup analyses. The red horizontal line represents the prediction interval.
3.8. Prevalence of Invasive Group B Streptococcus Cases
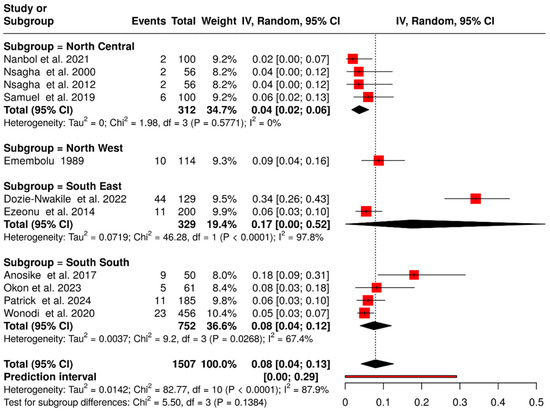
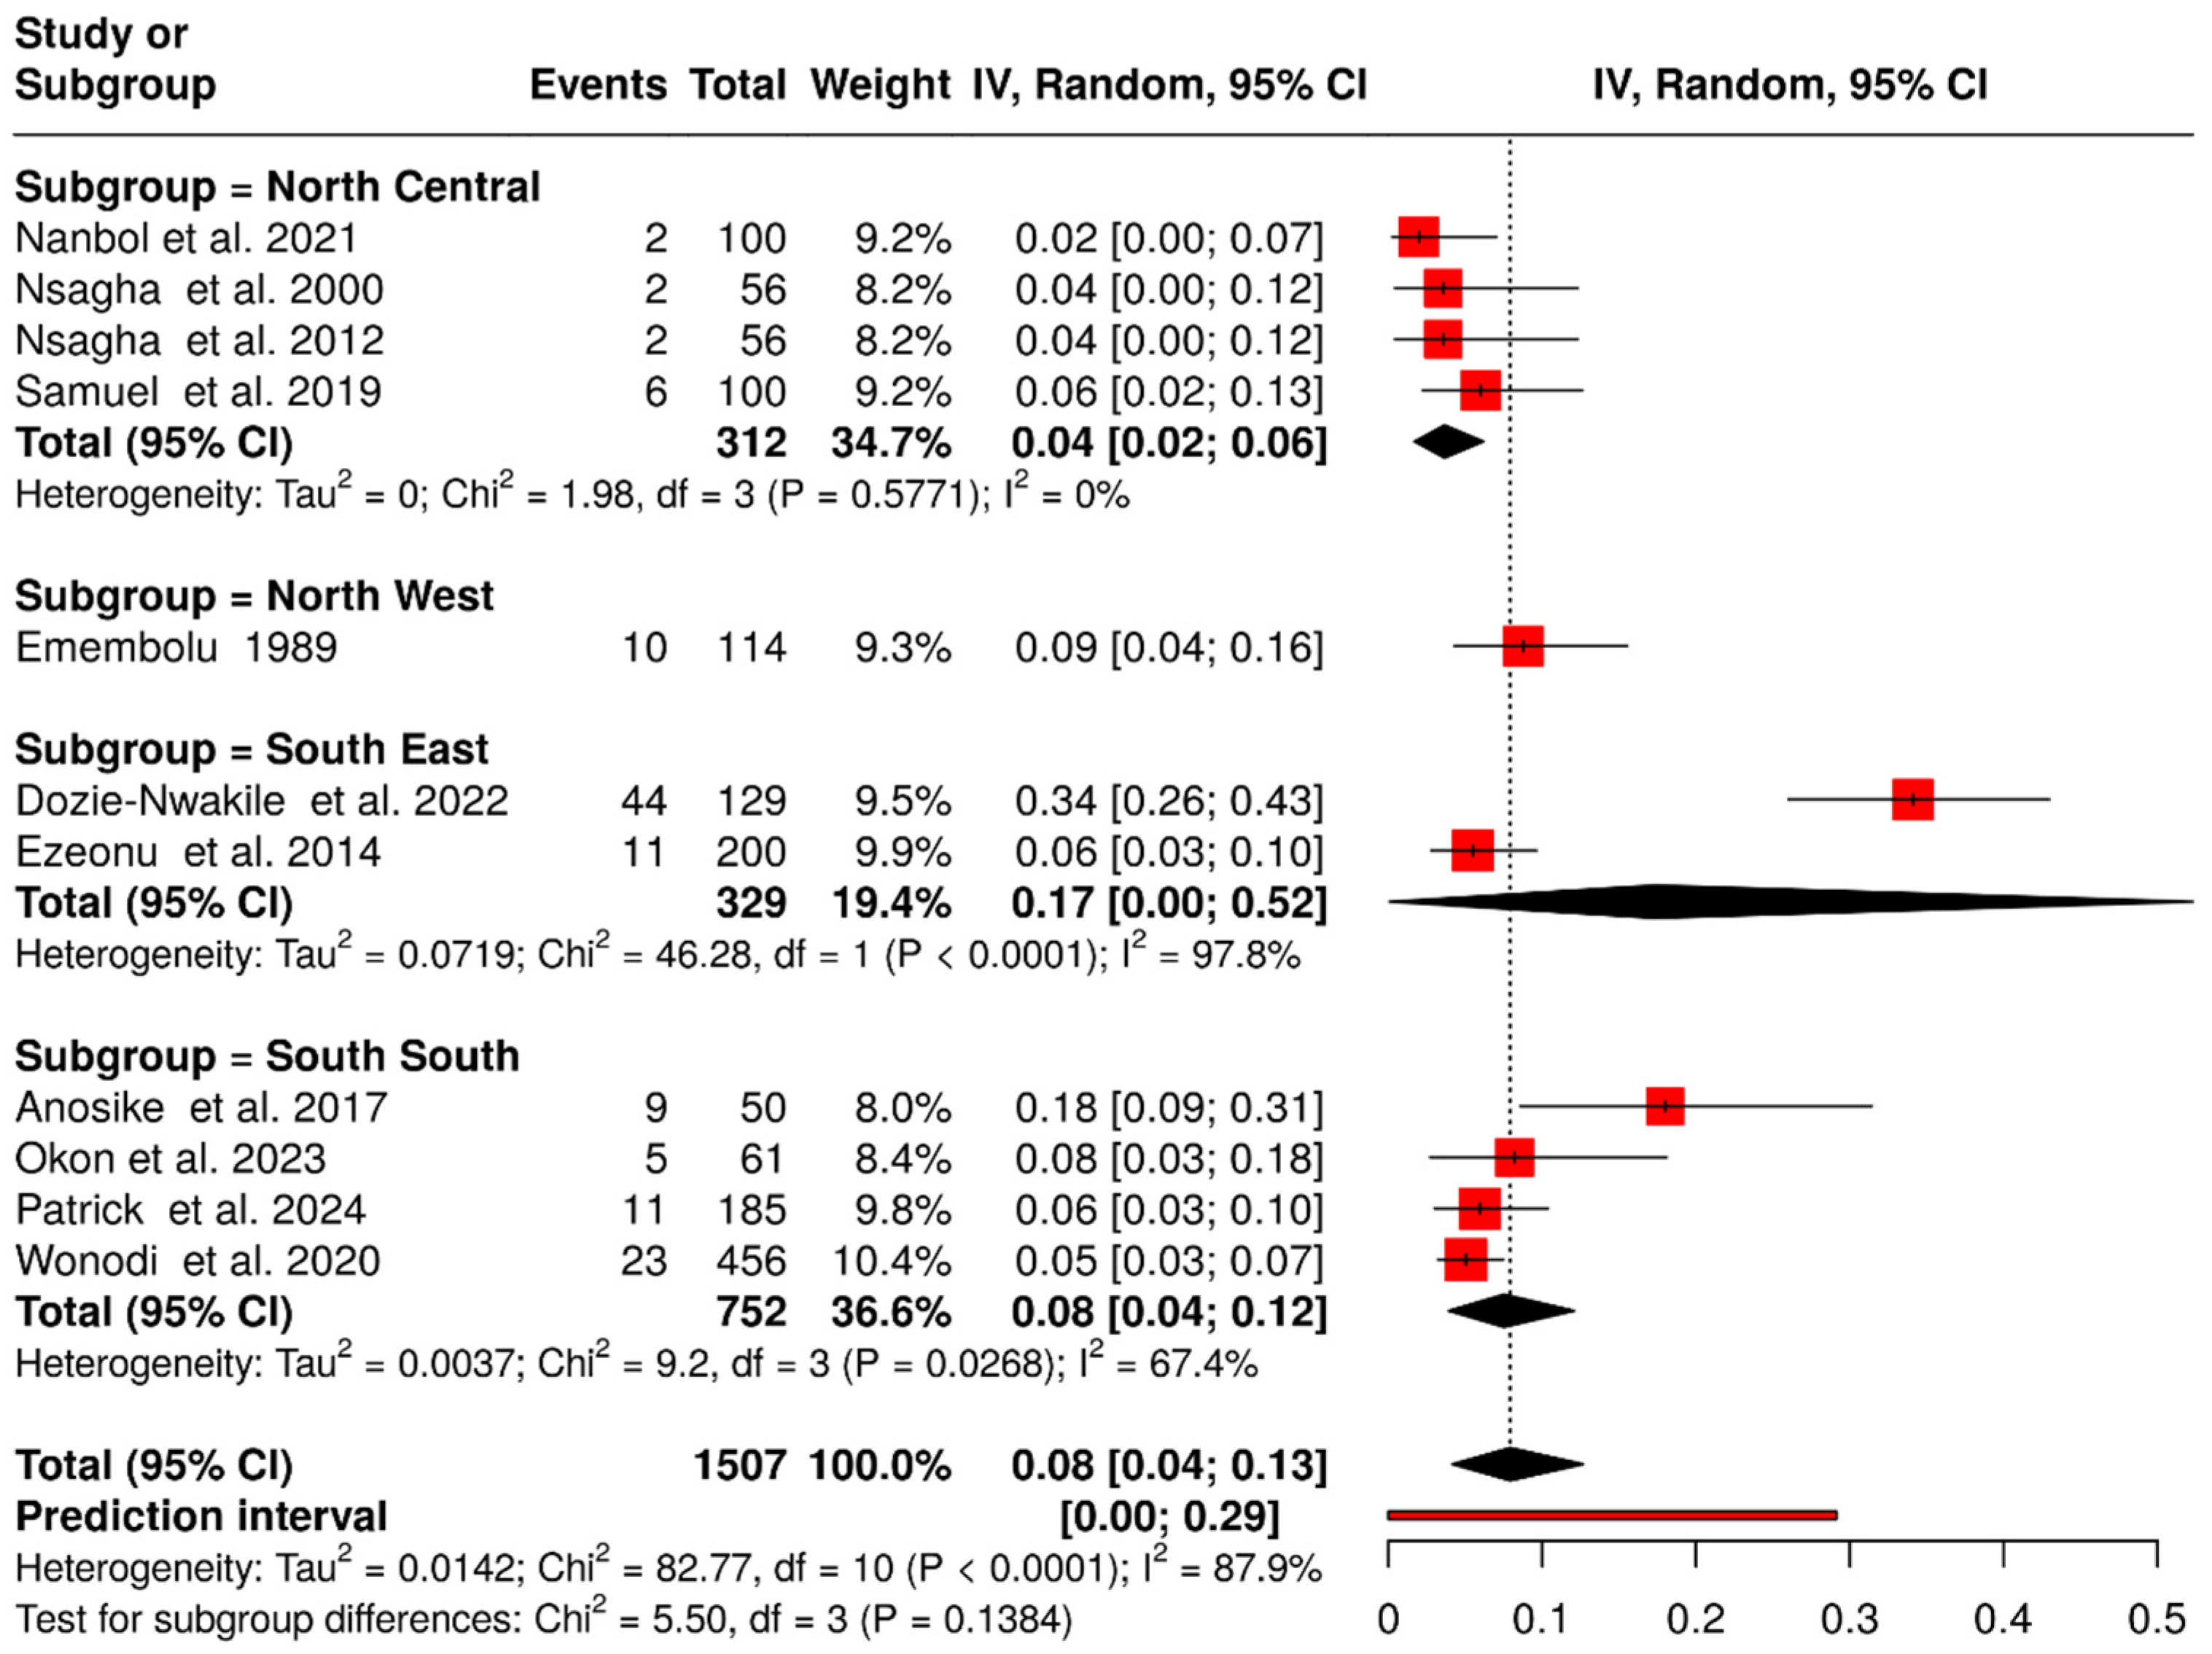
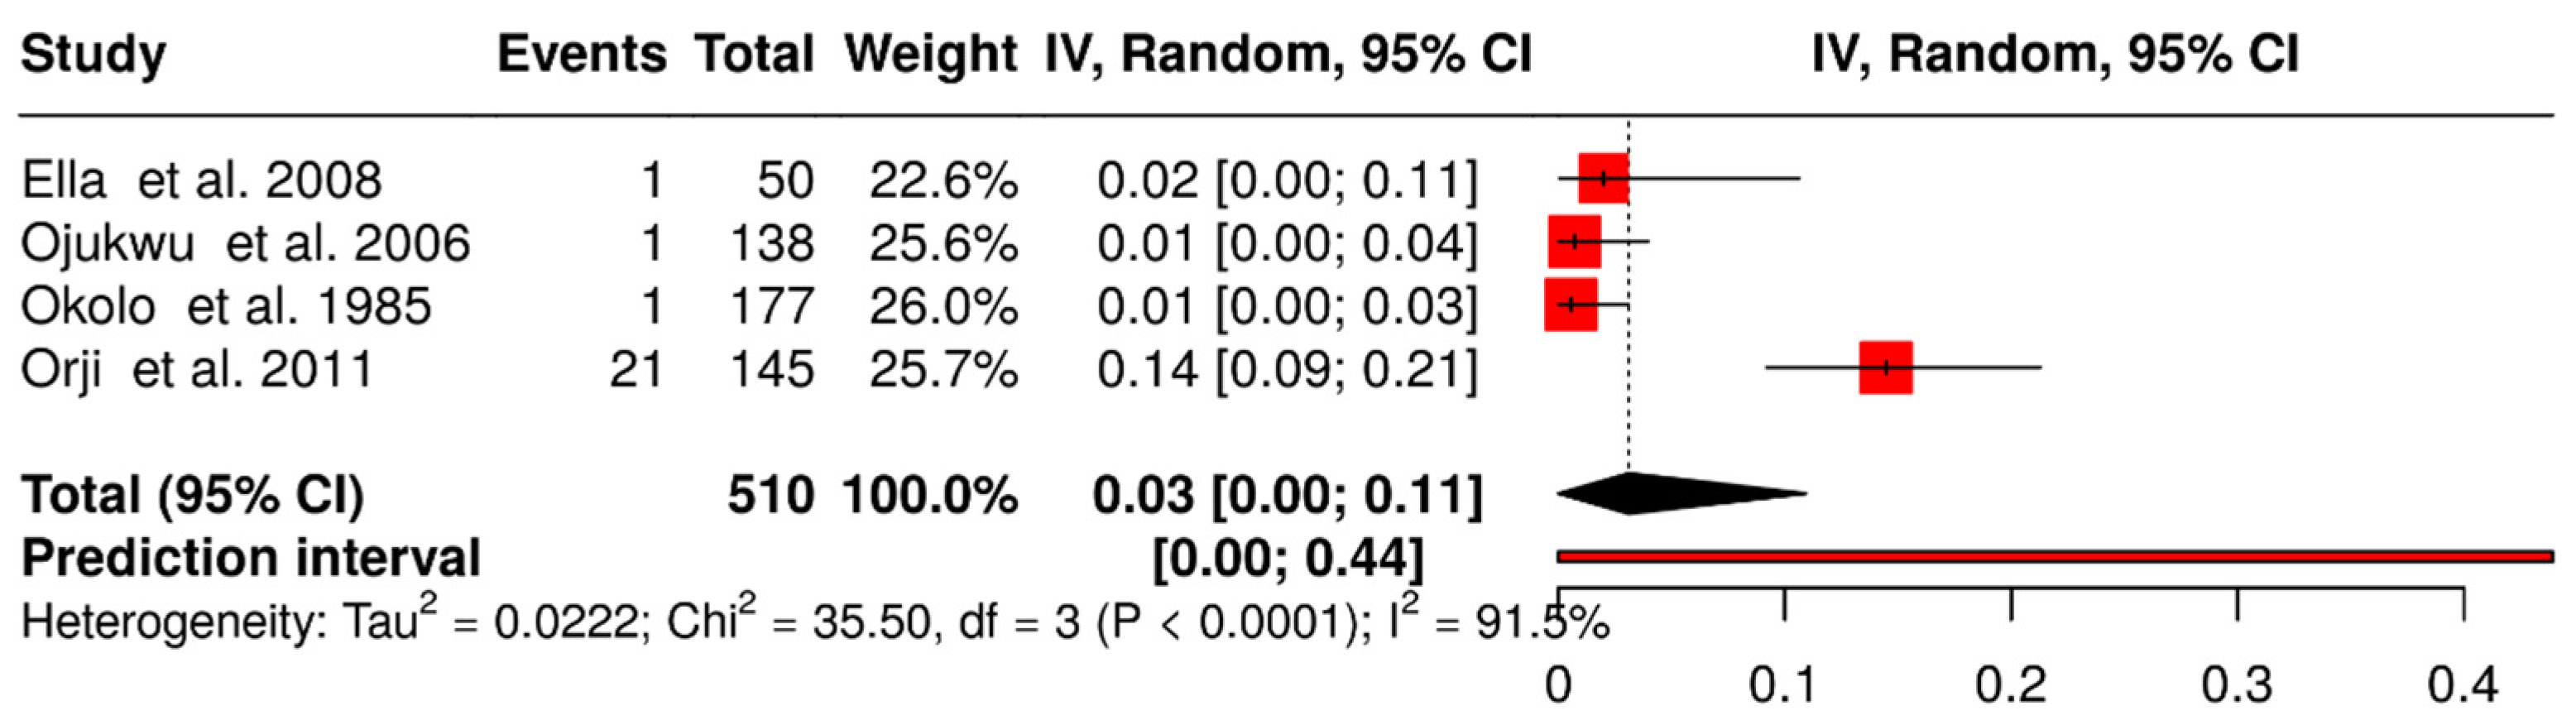
Four studies out of the 43 included studies in this review reported invasive GBS in Nigeria, with an overall pooled prevalence of 3.0% (95% CI: 0.0–11.0%) (Figure 9) [39,51,52,58]. Interestingly, all occurred in neonates. In Kaduna, GBS was isolated from 1 of 50 neonates with sepsis (7.69%) [39]. Ojukwu et al. [51] and Okolo and Omene [52] each identified one case of neonatal septicaemia, with overall incidences of 7.98 and 5.6 per 1000 live births, respectively. In Rivers State, GBS was detected in 21 of 145 infant blood or cerebrospinal fluid samples (14.5%) [58].
Figure 9.
Forest plot of prevalence of invasive GBS infection in Nigeria (1984–2024). The pooled prevalence was estimated using random-effects models [39,51,52,58]. Each black horizontal line represents a study’s 95% confidence interval, with red squares indicating point estimates and weights. Black diamonds denote comparisons, while dotted or dashed lines show subgroup analyses. The red horizontal line represents the prediction interval.
3.9. Capsular Serotype Distribution of Group B Streptococcus in Nigeria
Of the 43 included studies, seven reported capsular serotype distribution [12,17,33,34,37,43,61]. Of these, four studies were included in the analysis, while three were excluded: two (Hoppe et al. [43] and Kwatra et al. [12]) had unclear serotype data, and one (Bob-Manuel et al. [34]) performed serotyping on isolates that had already been classified. Across the four studies, 356 GBS isolates were serotyped. The most common identified serotype was serotype V (137, 38.5%). Others include serotype II (78, 21.9%), serotype Ia (63, 17.7%), serotype III (53, 14.9%), serotype Ib (10, 2.8%), serotype IV (7, 2.0%), serotype VI (1, 0.3%), and non-typeable (NT) isolates (7, 2.0%).
Individual studies showed variable distributions. Samuel et al. [61] observed serotype Ia (42.1%), III (31.6%), V (15.8%), and II (10.5%). Elikwu et al. [37] reported serotype Ia (23.9%) predominating in maternal isolates and serotype II (71.4%) in neonates. Bob-Manuel et al. [33] identified serotype V (32.6%) and serotype Ia (21.7%) as most common among pregnant women, while Medugu et al. [17] reported serotype V (45.7%), II (24.5%), Ia (13.9%), III (11.8%), NT (2.9%), and IV (1.2%).
3.10. Sequence Type Distribution of Group B Streptococcus
Two studies reported MLST data in Nigeria [17,34], identifying 14 STs. The combined STs from both studies included ST19 (N = 18, 26.5%), ST182 (N = 10, 14.7%), ST28 (n = 6, 8.8%), ST1, ST24, and ST486 (N = 5 each, 7.4%), ST17 and ST23 (N = 4 each, 5.9%), ST2 (N = 3, 4.4%), ST8, ST26, and ST1336 (N = 2 each, 2.9%), and ST196 and ST762 (N = 1 each, 1.5%).
Individually, Medugu et al. in 2017 reported STs included ST19 (N = 9, 25.7%), ST182 (N = 7, 20.0%), ST1 (N = 4, 11.4%), ST28, ST17, and ST23 (N = 3 each, 8.6%), and ST2, ST196, ST8, ST26, ST24, and ST762 (N = 1 each, 2.9%) [17]. Similarly, Bob-Manuel et al. (2021) reported 12 STs: ST19 (N = 9, 27.3%), ST486 (N = 5, 15.2%), ST24 (N = 4, 12.1%), ST28 and ST182 (N = 3 each, 9.1%), ST2 and ST1336 (N = 2 each, 6.1%), and ST1, ST8, ST17, ST23, and ST26 (N = 1 each, 3.0%) [34].
4. Discussion
GBS is a significant pathogen of public health importance, widely recognized as both a neonatal and maternal pathogen. Globally, colonization varies by geography and socioeconomic context [2,6,7,16,65]. Our meta-analysis found an overall prevalence of 12.0% (95% CI: 9.0–15.0%) in Nigeria, with neonatal colonization at 16.0% (95% CI: 12.0–22.0%), maternal colonization at 13.0% (95% CI: 9.0–16.0%), and 8.0% (95% CI: 4.0–13.0%) in non-pregnant populations. These figures highlight Nigeria’s contribution to the global GBS burden and illustrate regional variation that requires contextual interpretation.
The 16.0% neonatal colonization rate is concerning compared with global and African estimates [2,66,67,68]. A higher prevalence in northern Nigeria (19.0%) compared to the south (16.0%), this may suggest differences in the dynamics of vertical transmission. Invasive neonatal disease was detected in 3.0% (95% CI: 0.0–11.0%), consistent with global trends [2,66]. Although neonatal GBS is under-documented in Nigeria, our findings support its role in early-onset sepsis [45,65,69]. Africa bears the highest global incidence (1.12 per 1000 live births vs. 0.49 per 1000 globally) [67], and Nigerian data align with this pattern [12,17,39,51,52,58,67].
The maternal prevalence in Nigeria was 13.0%, which is lower than the global estimate of 18% (95% CI: 17–19%) [6] and lower than the average rates in other African countries (16–22%) [7,14,15,65]. Methodological variation, such as swab site, timing, culture techniques, and sample size, likely contributed to this lower pooled prevalence [7,62]. Regionally, rates were higher in the south (14%) compared to the north (11%), mirroring the broader continental heterogeneity [9,16,70,71]. GBS colonization in HIV-positive pregnant women has been examined in multiple studies from different countries [71,72,73]. Among HIV-positive pregnant women, prevalence was 11.0% (95% CI: 3.0–25.0%) with no significant association between HIV and colonization (OR = 1.47, 95% CI: 0.66–3.24). This aligns with findings from Malawi (19.4% vs. 21.7%), Brazil (19.8% vs. 14.15%), Belgium (29.6% vs. 24.2%), and the United States (41.3% vs. 30.6%) [74,75,76,77], although data from Tanzania suggest an increased risk (63.1% vs. 18.9%) [73]. Given the wide confidence intervals and few Nigerian studies, larger, prospective cohorts are needed to clarify this relationship [18,32,47].
Beyond neonates and pregnant women, GBS is also an important pathogen on the broader population [4,8,78,79,80]. Globally, it has been reported in different forms of infection, including throat infections in school-aged children and young adults [63,81,82], urinary tract infections in men and women, and even infertility [40,83,84,85] and sepsis and cellulitis [79,80]. Our pooled prevalence among this population was 8.0%, comparable to global estimates (9–32%) [4,78,86,87,88]. Nigerian data fall within the lower range of global values, although regional differences were evident, with a higher prevalence in the south (11%) compared to the north (5%).
The serotype distribution in Nigeria reflects the global epidemiology. Across the five studies that conducted serotyping, serotype V was predominant [12,17,33,37,43]. These, along with serotypes Ia, Ib, II, and III, account for over 90% of invasive cases globally and are targets of candidate maternal vaccines [7,14,67]. There is considerable variation in GBS serotype distribution across countries. Kwatra et al. reported serotype Ia as the most prevalent in Bangladesh, India, Ethiopia, Kenya, and South Africa, serotype V in Mali, and serotype III in Mozambique [12]. In Southeast Asian countries, Muthanna and colleagues identified serotype III as the predominant serotype, followed by serotypes V, II, VI, and Ia [6]. In Europe, North America, and Southern Africa, serotype IV was more commonly reported, whereas serotype V predominated in West Africa [11].
Like other African countries, there are limited GBS MLST data in Nigeria. Two studies, Medugu et al. and Bob-Manuel et al., conducted MLST, reporting 14 GBS STs with ST19 (26.5%), ST182 (14.7%), and ST28 (8.8%) predominated [17,34]. In Kenya, ST17 and ST23 were the most reported, followed by ST10 and ST1. In Senegal, ST1, ST26, and ST28 were the most common [89,90]. Outside Africa, studies from Malaysia and Thailand indicate ST1 as the most prevalent STs, followed by ST17 and ST283 [6,91,92]. A Canadian study similarly reported ST1 as the most common, followed by ST23 [93]. Unlike regions where hypervirulent ST17 dominates, Medugu et al. and Bob-Manuel et al. reported low (5.9%). The availability of only two MLST studies in Nigeria highlights the need for expanded molecular epidemiology. Without additional data, it is difficult to track the circulation and evolution of GBS strains or assess their potential virulence in Nigeria. Expanded surveillance, including MLST or whole-genome sequencing, would provide critical information on STs, clonal complexes and virulence factors, helping to guide vaccine implementation and public health strategies in Nigeria [11,17,94].
Nigeria’s 13% maternal colonization prevalence suggests opportunities for prevention. In high-income countries, universal screening and IAP have reduced EOD [1,5]. While universal screening may be impractical in Nigeria, risk-based or culture-limited approaches could be introduced in tertiary centers [17,95]. The cost of implementing screening (₦300,000/500 women) is substantially lower than treating neonatal sepsis or its sequelae [17]. Standardized rectovaginal swabs, improved culture capacity, and national perinatal pathogen surveillance are essential. Antenatal care should be updated to clarify and include IAP. Preparations for maternal GBS vaccines should include monitoring of serotype and lineage, particularly in under-studied northern and rural states.
This study addresses an important question and represents the first systematic review and meta-analysis of GBS in Nigeria. By pooling data from pregnant women, neonates, non-pregnant adults, and HIV-positive populations, it provides a broad national overview. Methodological rigor, adherence to PRISMA, and sensitivity analyses further strengthen the reliability of findings. However, high heterogeneity (I2 > 90%) across studies, reflecting differences in methods, swab sites, and culture techniques, limits comparability. Study quality was assessed using the JBI checklists; however, a formal GRADE assessment was not conducted. Similarly, differences in rates may reflect variation in surveillance, screening, and research coverage rather than true biological differences, as only 19 of 37 states contributed data, leaving significant geographical gaps. Most data came from urban hospital settings, which may have led to an underestimation of rural prevalence.
Overall, the findings suggest that GBS colonization and disease are underrecognized in Nigeria, and the prevalence should be interpreted with caution, as it does not reflect uniform national coverage. They emphasize the need to enhance standardized GBS screening and diagnostic capabilities in maternal and neonatal care, supported by national guidelines and coordinated surveillance, to address existing geographical disparities. Future research should focus on multi-state, population-based studies and greater inclusion of rural populations to better inform prevention and control strategies.
5. Conclusions
This systematic review synthesizes four decades of GBS data in Nigeria, revealing an overall prevalence of 12%, higher in neonates (16%) than in pregnant women (13%) or other populations (8%). Findings align with global trends in serotypes and STs although hypervirulent ST17 appears to be less prevalent. Expanding surveillance, introducing feasible prevention measures, and preparing for maternal vaccines are vital steps to address neonatal invasive infections and strengthen maternal–child health outcomes.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/medsci14010093/s1, Table S1: PRISMA Checklist; Table S2: Search Queries; Table S3: Excluded Articles with Reasons [69,96,97,98,99,100,101,102,103,104,105,106,107,108,109,110,111,112,113,114,115,116]; Table S4: Quality Assessment of Included Studies; Table S5: Publication Bias Assessment Result; Table S6: Odds ratios (OR) of GBS colonization by maternal HIV status in Nigeria.
Author Contributions
Conceptualization, A.A. and S.A.-N.; methodology, A.A., V.A.A., B.H.G. and S.A.-N.; data curation, A.A. and V.A.A.; formal analysis, A.A., V.A.A. and S.A.-N.; investigation, A.A., V.A.A., A.M. and B.H.G.; project administration, S.A.-N.; resources, V.A.A., M.N.M.D., M.H.Y. and S.A.-N.; supervision, S.A.-N.; validation, V.A.A. and S.A.-N.; visualization, A.A. and B.H.G.; writing—original draft preparation, A.A.; writing—review and editing, A.A., V.A.A., A.M., B.H.G., M.H.Y., M.N.M.D. and S.A.-N. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article/Supplementary Material. Further inquiries can be directed to the corresponding authors.
Acknowledgments
The authors gratefully acknowledge the support of the Queen Elizabeth Commonwealth Scholarship (QECS) managed by the Association of Commonwealth Universities (ACU).
Conflicts of Interest
The authors declare no competing interests.
Abbreviations
The following abbreviations are used in this manuscript:
| GBS | Group B Streptococcus |
| PROSPERO | International Prospective Register of Systematic Reviews |
| PRISMA | Preferred Reporting Items for Systematic reviews and Meta-Analyses |
| MLST | Multilocus Sequence Typing |
| ST | Sequence Type |
| HIV | Human Immunodeficiency Virus |
| IAP | Intrapartum Antibiotic Prophylaxis |
| EOD | Early-Onset Disease |
| OR | Odd Ratio |
| CI | Confidence Interval |
References
- World Health Organization. Group B Streptococcus Vaccine: Full Value Vaccine Assessment. Available online: https://www.who.int/publications/i/item/9789240037526 (accessed on 6 January 2025).
- Gonçalves, B.P.; Procter, S.R.; Paul, P.; Chandna, J.; Lewin, A.; Seedat, F.; Koukounari, A.; Dangor, Z.; Leahy, S.; Santhanam, S.; et al. Group B Streptococcus Infection during Pregnancy and Infancy: Estimates of Regional and Global Burden. Lancet Glob. Health 2022, 10, e807–e819. [Google Scholar] [CrossRef] [Scilit]
- Francois Watkins, L.K.; McGee, L.; Schrag, S.J.; Beall, B.; Jain, J.H.; Pondo, T.; Farley, M.M.; Harrison, L.H.; Zansky, S.M.; Baumbach, J.; et al. Epidemiology of Invasive Group B Streptococcal Infections Among Nonpregnant Adults in the United States, 2008–2016. JAMA Intern. Med. 2019, 179, 479. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bliss, S.J.; Manning, S.D.; Tallman, P.; Baker, C.J.; Pearlman, M.D.; Marrs, C.F.; Foxman, B. Group B Streptococcus Colonization in Male and Nonpregnant Female University Students: A Cross-Sectional Prevalence Study. Clin. Infect. Dis. 2002, 34, 184–190. [Google Scholar] [CrossRef] [Scilit]
- Behjati, S.; Prentice, P.; Rennie, J. Management of Group B Streptococcal Sepsis Risk in Well, Term Newborns. Acta Paediatr. 2012, 101, 128–131. [Google Scholar] [CrossRef] [Scilit]
- Muthanna, A.; Sulaiman, N.; Dzaraly, N.D.; Al-Obaidi, M.M.J.; Amin-Nordin, S.; Azmai, M.N.A.; Desa, M.N.M. Distribution of Group B Streptococcus Isolated from Humans in Southeast Asia: A Systematic Review and Meta-Analysis. Asian Pac. J. Trop. Med. 2025, 18, 289–301. [Google Scholar] [CrossRef] [Scilit]
- Russell, N.J.; Seale, A.C.; O’Driscoll, M.; O’Sullivan, C.; Bianchi-Jassir, F.; Gonzalez-Guarin, J.; Lawn, J.E.; Baker, C.J.; Bartlett, L.; Cutland, C.; et al. Maternal Colonization with Group B Streptococcus and Serotype Distribution Worldwide: Systematic Review and Meta-Analyses. Clin. Infect. Dis. Off. Publ. Infect. Dis. Soc. Am. 2017, 65, S100–S111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Navarro-Torné, A.; Curcio, D.; Moïsi, J.C.; Jodar, L. Burden of Invasive Group B Streptococcus Disease in Non-Pregnant Adults: A Systematic Review and Meta-Analysis. PLoS ONE 2021, 16, e0258030. [Google Scholar] [CrossRef] [Scilit]
- Wang, J.; Zhang, Y.; Lin, M.; Bao, J.; Wang, G.; Dong, R.; Zou, P.; Chen, Y.; Li, N.; Zhang, T.; et al. Maternal Colonization with Group B Streptococcus and Antibiotic Resistance in China: Systematic Review and Meta-Analyses. Ann. Clin. Microbiol. Antimicrob. 2023, 22, 5. [Google Scholar] [CrossRef] [Scilit]
- Kao, Y.; Tsai, M.-H.; Lai, M.-Y.; Chu, S.-M.; Huang, H.-R.; Chiang, M.-C.; Fu, R.-H.; Lu, J.-J.; Hsu, J.-F. Emerging Serotype III Sequence Type 17 Group B Streptococcus Invasive Infection in Infants: The Clinical Characteristics and Impacts on Outcomes. BMC Infect. Dis. 2019, 19, 538. [Google Scholar] [CrossRef] [Scilit]
- Bianchi-Jassir, F.; Paul, P.; To, K.-N.; Carreras-Abad, C.; Seale, A.C.; Jauneikaite, E.; Madhi, S.A.; Russell, N.J.; Hall, J.; Madrid, L.; et al. Systematic Review of Group B Streptococcal Capsular Types, Sequence Types and Surface Proteins as Potential Vaccine Candidates. Vaccine 2020, 38, 6682–6694. [Google Scholar] [CrossRef] [Scilit]
- Kwatra, G.; Izu, A.; Cutland, C.; Akaba, G.; Ali, M.M.; Ahmed, Z.; Beck, M.M.; Barsosio, H.C.; Berkley, J.A.; Chaka, T.E.; et al. Prevalence of Group B Streptococcus Colonisation in Mother–Newborn Dyads in Low-Income and Middle-Income South Asian and African Countries: A Prospective, Observational Study. Lancet Microbe 2024, 5, 100897. [Google Scholar] [CrossRef] [Scilit]
- Lee, K.W.; Yap, S.F.; Murdan, S.; Zainudin, Z.; Abdul Hamid, H.; Emamjomeh, M.; Mohd Desa, M.N.; Sither Joseph, N.M.; Azmai Amal, M.N.; Amin-Nordin, S. Maternal and Neonatal Group B Streptococcus Colonisation: A Systematic Review and the Meta-analysis of Matched-pair Studies. Acta Paediatr. 2024, 113, 892–911. [Google Scholar] [CrossRef] [Scilit]
- Gizachew, M.; Tiruneh, M.; Moges, F.; Tessema, B. Streptococcus agalactiae Maternal Colonization, Antibiotic Resistance and Serotype Profiles in Africa: A Meta-Analysis. Ann. Clin. Microbiol. Antimicrob. 2019, 18, 14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wadilo, F.; Hailemeskel, E.; Kedir, K.; El-Khatib, Z.; Asogba, P.C.; Seyoum, T.; Landis, F.C.; Howe, R.; Boltena, M.T. Prevalence of Group B Streptococcus Maternal Colonization, Serotype Distribution, and Antimicrobial Resistance in Sub-Saharan Africa: A Systematic Review and Meta-Analysis. J. Glob. Antimicrob. Resist. 2023, 32, 134–144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kyohere, M.; Davies, H.G.; Karampatsas, K.; Cantrell, L.; Musoke, P.; Nakimuli, A.; Tusubira, V.; Nsimire, J.S.; Jamrozy, D.; Khan, U.B.; et al. Epidemiology of Group B Streptococcus: Maternal Colonization and Infant Disease in Kampala, Uganda. Open Forum Infect. Dis. 2025, 12, ofaf167. [Google Scholar] [CrossRef] [Scilit]
- Medugu, N.; Iregbu, K.C.; Parker, R.E.; Plemmons, J.; Singh, P.; Audu, L.I.; Efetie, E.; Davies, H.D.; Manning, S.D. Group B Streptococcal Colonization and Transmission Dynamics in Pregnant Women and Their Newborns in Nigeria: Implications for Prevention Strategies. Clin. Microbiol. Infect. 2017, 23, 673.e9–673.e16. [Google Scholar] [CrossRef] [Scilit]
- Makinde, O.; Okusanya, B.O.; Osanyin, G. Group B Streptococcus Vaginal Colonization in Pregnant Women Living with HIV Infection: Prevalence and Antibiotic Susceptibility at HIV Referral Centers in Lagos, Nigeria. J. Matern. Fetal Neonatal Med. 2022, 35, 9098–9104. [Google Scholar] [CrossRef] [Scilit]
- Healthy Newborn Network—Nigeria. Available online: https://healthynewbornnetwork.org/country/nigeria/ (accessed on 25 October 2025).
- Adesola, R.O.; Opuni, E.; Idris, I.; Okesanya, O.J.; Igwe, O.; Abdulazeez, M.D.; Lucero-Prisno, D.E. Navigating Nigeria’s Health Landscape: Population Growth and Its Health Implications. Environ. Health Insights 2024, 18, 11786302241250211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akadri, A.A.; Osuolale, B.D.; Shorunmu, T.O.; Odelola, O.I. Group B Streptococcus Colonization in Pregnancy: Prevalence, Determinants and Antibacterial Susceptibility Pattern in Sagamu, Nigeria. J. Adv. Med. Med. Res. 2019, 29, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Bello, O.; Kehinde, A.; Oluwasola, T.; Olakogbe, A. Prevalence of Rectovaginal Group B Streptococcus (GBS) among Pregnant Women at University College Hospital, Ibadan, Nigeria. Trop. J. Obstet. Gynaecol. 2016, 33, 21–26. [Google Scholar]
- Anosike, I.; Ebana, R.; Edet, U.; Egbomuche, R.; Victory, A. Prevalence of Streptococcus agalactiae among Women Resident in Calabar, Cross River State, Nigeria. Asian J. Res. Med. Pharm. Sci. 2017, 2, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Nsagha, D.S.; Kamga, H.L.F.; Assob, J.C.N.; Njunda, A.L.; Bello, C.S.S.; Kandakai-Olukemi, Y.T. Epidemiological Significance of the Colonization of Streptococcus agalactiae in the Anorectum and Endocervix of Non-Parturients in Jos, Nigeria. Afr. J. Clin. Exp. Microbiol. 2012, 13, 144–149. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 Statement: An Updated Guideline for Reporting Systematic Reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan—A Web and Mobile App for Systematic Reviews. Syst. Rev. 2016, 5, 210. [Google Scholar] [CrossRef] [Scilit]
- Hilton, M. JBI Critical Appraisal Checklist for Systematic Reviews and Research Syntheses (Product Review). J. Can. Health Libr. Assoc. J. Assoc. Bibl. Santé Can. 2024, 45, 180–183. [Google Scholar] [CrossRef] [Scilit]
- Fekete, J.T.; Győrffy, B. MetaAnalysisOnline.Com: Web-Based Tool for the Rapid Meta-Analysis of Clinical and Epidemiological Studies. J. Med. Internet Res. 2025, 27, e64016. [Google Scholar] [CrossRef] [Scilit]
- Akinlolu, J.; Omololu, A.J.; Owolabi, A.; Omololu, A.O. Molecular Epidemiological Status of Group B Streptococcus in Ile Ife South Western Nigeria. Arch. Med. 2018, 10, 4. [Google Scholar] [CrossRef] [Scilit]
- Akinniyi, A.; Adesiyun, A.; Kolawole, A.; Giwa, F.; Randawa, A. The Prevalence of Asymptomatic Group B Streptococcal Infection and Antimicrobial Sensitivity Pattern among Parturients at Ahmadu Bello University Teaching Hospital, Zaria, Nigeria. Trop. J. Obstet. Gynaecol. 2017, 34, 182. [Google Scholar] [CrossRef] [Scilit]
- Bamidele, A.O.; Adebayo, A.A.; Victoria, A.F.; Timothy, O.O.; Emmanuel, A.O.; Sunday, A.B.; Oluseyi, A.I.; Adewumi, B.; Olabisi, A.T.; Olumide, A.M. Correlates of Group B Streptococcal Colonization in Pregnancy at A Tertiary Hospital in South West Nigeria. Microbiol. Infect. Dis. 2022, 6, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Biobaku, R.O.; Olaleye, A.O.; Adefusi, O.F.; Adeyemi, B.A.; Onipede, A.O.; Loto, O.M.; Imaralu, J.O. Group B Streptococcus Colonization and HIV in Pregnancy: A Cohort Study in Nigeria. J. Neonatal Perinat. Med. 2017, 10, 91–97. [Google Scholar] [CrossRef] [Scilit]
- Bob-Manuel, M.; Stephenson, D.L.; Terhemen, K.; Ibinabo, L.O.; Orikomaba, K.O.; Kennedy, T.W. Epidemiology and Capsular Typing of Group B Streptococcus in Pregnant Women in Port Harcourt, Nigeria. Ann. Microbiol. Infect. Dis. 2021, 4, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Bob-Manuel, M.; McGee, L.; Igunma, J.A.; Alex-Wele, M.A.; Obunge, O.K.; Wariso, K.T. Whole Genome Sequence Based Capsular Typing and Antimicrobial Resistance Prediction of Group B Streptococcal Isolates from Colonized Pregnant Women in Nigeria. BMC Genom. 2021, 22, 627. [Google Scholar] [CrossRef] [Scilit]
- Dozie-Nwakile, O.C.; Nwakile, C.D.; Uchendu, I.K.; Okoroiwu, H.U.; Onyemelukwe, N.F. Prevalence, Characterization, Antimicrobial Susceptibility Pattern and Factors Associated with Group B Streptococci (Streptococcus agalactiae) from Clinical and Non-Clinical Sources in South-East Nigeria. J. Biol. Res. Boll. Della Soc. Ital. Biol. Sper. 2022, 95, 9922. [Google Scholar] [CrossRef] [Scilit]
- Egbule, O.S.; Enwa, O.F.; Omenogor, P.K.; Odum, E.I.; Iweriebor, B.C.; Obi, C.L. Multidrug Resistant Group B Streptococcus Isolates from Pregnant Women in Delta State, Nigeria. Pak. J. Biol. Sci. 2024, 27, 447–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elikwu, C.J.; Oduyebo, O.; Ogunsola, F.T.; Anorlu, R.I.; Okoromah, C.N.; König, B. High Group B Streptococcus Carriage Rates in Pregnant Women in a Tertiary Institution in Nigeria. Pan Afr. Med. J. 2016, 25, 249. [Google Scholar] [CrossRef] [Scilit]
- Elikwu, C.; Oduyebo, O.; Anorlu, R.; Konig, B. Antibiotic Susceptibility/Resistant Gene Profiles of Group B Streptococci Isolates from Pregnant Women in a Tertiary Institution in Nigeria. J. Clin. Sci. 2016, 13, 132. [Google Scholar] [CrossRef] [Scilit]
- Ella, E.; Ahmad, A.; Ogala, W.; Umoh, V.; Aliyu-Zubair, R. Bacteriology and Sensitivity Profile Bacterial Agents Responsible for Neonatal Septicaemia in aTertiary Hospital of Kaduna Metropolis. J. Pure Appl. Microbiol. 2008, 2, 103–108. [Google Scholar]
- Emembolu, J.O. Endometrial Flora of Infertile Women in Zaria, Northern Nigeria. Int. J. Gynaecol. Obstet. Off. Organ Int. Fed. Gynaecol. Obstet. 1989, 30, 155–159. [Google Scholar] [CrossRef] [Scilit]
- Ezeonu, I.M.; Agbo, M.C. Incidence and Anti-Microbial Resistance Profile of Group B Streptococcus (GBS) Infection in Pregnant Women in Nsukka, Enugu State, Nigeria. Afr. J. Microbiol. Res. 2014, 8, 91–95. [Google Scholar] [CrossRef] [Scilit]
- Gambo, A.U.; Mohammed, Y.; Abubakar, J.; Dada, K.M.; Shehu, I.M.; Bello, S.; Olasunmbo, Y. Asymptomatic Group B Streptococcal Infection, Antibiotic Sensitivity, Risk Factors and Pregnancy Outcome among Pregnant Women at the Usmanu Danfodiyo University Teaching Hospital, Sokoto, Nigeria. Int. J. Adv. Multidiscip. Res. Stud. 2024, 4, 698–703. [Google Scholar] [CrossRef] [Scilit]
- Hoppe, J.E.; Grieshaber, J.; Höfler, W. Colonization of Nigerian Neonates with Group B Streptococci and Its Rapid Detection. Infection 1986, 14, 74–78. [Google Scholar] [CrossRef] [Scilit]
- Ibrahim, U.A.; Panti, A.A.; Mohammed, Y.; Tunau, K.A.; Asma’u, A.; Abubakar, J.G.; Ladan, A.A. Risk Factors for Group B Streptococcus Colonization and Drugs Sensitivity Pattern in a Nigerian Obstetric Population. Open J. Obstet. Gynecol. 2021, 11, 804–814. [Google Scholar] [CrossRef]
- Idih, E.; Ezem, B.; Onyegbule, O.; Ododo, N.; Onumajuru, C. Prevalence of Vaginal Group-B-Streptococcus, Antibiotic and Antigen Sensitivity amongst Parturients at the Federal Medical Center Owerri, Nigeria. Niger. J. Med. 2019, 28, 5. [Google Scholar] [CrossRef] [Scilit]
- Nanbol, H.D.; Listick, N.D.; Binshak, N.; Olukemi-Kandakai, Y.T.; Samuel, D.A.; Dangana, A.; Issaoui, R.; Abdullahi, I.N. Streptococcus agalactiae Carriage, Serotype Distribution and Associated Antibiogram among Pregnant and Non-Pregnant Women in Jos City, Nigeria. Niger. Med. J. 2021, 62, 249–259. [Google Scholar] [CrossRef] [Scilit]
- Njoku, C.; Emechebe, C.; Agbakwuru, A. Prevalence and Determinants of Anogenital Colonization by Group B Streptococcus Infection Among HIV Positive and Negative Women in Calabar, Nigeria. Int. J. Women’s Health Reprod. Sci. 2018, 6, 11–17. [Google Scholar] [CrossRef] [Scilit]
- Nsagha, D.; Bello, C.; Kandakai-Olukemi, Y. Hippurate Hydrolysis and Christie, Atkins, Munch-Peterson Tests Epidemiological Diagnostic Tools for Streptococcus agalactiae Carriage in Pregnancy. East Afr. Med. J. 2000, 77, 34–36. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nwachukwu, N.; Utsalo, S.; Kanu, I.; Anyanwu, E. Genital Colonization of Group B Streptococcus at Term Pregnancy in Calabar, Nigeria. Internet J. Pediatr. Neonatol. 2007, 7, 2. [Google Scholar] [CrossRef] [Scilit]
- Ojo, O.O.; Awonuga, D.O.; Dedeke, I.O.F.; Nwadike, V.U.; Adenaya, O.R.; Odelola, O.I. Prevalence of Group B Streptococcus Colonisation and Antimicrobial Susceptibility Pattern among Pregnant Women Attending a Tertiary Health Facility in Ogun State, Southwest Nigeria. J. West Afr. Coll. Surg. 2019, 9, 8–14. [Google Scholar] [CrossRef] [Scilit]
- Ojukwu, J.U.; Abonyi, L.E.; Ugwu, J.; Orji, I.K. Neonatal Septicemia in High Risk Babies in South-Eastern Nigeria. J. Perinat. Med. 2006, 34, 166–172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Okolo, A.A.; Omene, J.A. Changing Pattern of Neonatal Septicaemia in an African City. Ann. Trop. Paediatr. 1985, 5, 123–126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Okon, K.; Usman, H.; Usman, Z.; Balogun, S. Prevalence of Group B Streptococcus (GBS) Colonization among Pregnant Women Attending Antenatal Clinic of a Tertiary Hospital in Northeastern, Nigeria. Am. J. Res. Commun. 2013, 1, 54–66. [Google Scholar]
- Okon, R.-S.; Onwuezobe, I.; Edem, E.-N.; Akereuke, U.-E.; Bonne, S.; Bawonda, E.-O. Bacterial Aetiologic Profile and Antibiotic Response Patterns of Lower Respiratory Tract Infection (LRTI) among HIV/AIDS Patients on Highly Active Antiretroviral Therapy (HAART) in Uyo, South-South Nigeria. Acta Microbiol. Hell. 2023, 68, 185–195. [Google Scholar] [CrossRef]
- Olanisebe, S.B.; Adetosoye, A.I. Determination of Asymptomatic Carrier Rate of Beta-Haemolytic Group B Streptococcus in Vaginas of Pregnant Women in Ibadan, Nigeria. Zentralbl. Bakteriol. Mikrobiol. Hyg. A 1986, 261, 248–253. [Google Scholar] [CrossRef] [Scilit]
- Onipede, A.; Adefusi, O.; Adeyemi, A.; Adejuyigbe, E.; Oyelese, A.; Ogunniyi, T. Group B Streptococcus Carriage during Late Pregnancy in Ile-Ife, Nigeria. Afr. J. Clin. Exp. Microbiol. 2012, 13, 135–143. [Google Scholar] [CrossRef] [Scilit]
- Onwuezobe, I.; Effiom, R. Prevalence and Associated Risk Factors of Group B Streptococcus in Pregnant Women Attending Antenatal Care in a Nigerian Urban Hospital. Ibom Med. J. 2016, 9, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Orji, F.; Nwachukwu, N.; Iheukwumere, I.; Emeana, U. Group B Streptococcal (GBS) Infections among Infants in Port Harcourt City, Nigeria. Aust. J. Basic Appl. Sci. 2011, 5, 1114–1118. [Google Scholar]
- Patrick, E.E.; Kenneth, I.E.P.; Ifeoma, A.V.; Akpomedaye, S. Prevalence of Group B Streptococcus among Individuals in Yenagoa, Bayelsa State, South South, Nigeria. Afr. J. Med. Surg. Public Health Res. 2024, 1, 54–65. [Google Scholar] [CrossRef] [Scilit]
- Rotimi, V.O.; Olowe, S.A.; Ahmed, I. The Development of Bacterial Flora of Premature Neonates. J. Hyg. 1985, 94, 309–318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Samuel, D.A.; Egah, D.Z.; Yvonne, K.-O.T. Prevalence of Streptococcus agalactiae Serotypes Associated with Anogenital Colonization among Pregnant Women in Jos. J. Adv. Med. Med. Res. 2019, 29, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Uhiara, J.E. Group B Streptococcal Carriage among Parturients and Their Neonates in Zaria, Nigeria. Afr. J. Med. Med. Sci. 1993, 22, 79–83. [Google Scholar] [PubMed]
- Wonodi, W. Prevalence and Pattern of Beta-Haemolytic Streptococcal Throat Infections among Primary School Children in a Rural Community in Rivers State. Port Harcourt Med. J. 2020, 14, 23–30. [Google Scholar] [CrossRef] [Scilit]
- Yerumoh, S.; Alenoghena, I.; Isabu, P.; Adewusi, G. Risk Factors for Group B Streptococcal Infection among Women Attending Antenatal Clinic in a Tertiary Health Institution in Edo State, Nigeria. Sub Sahar. Afr. J. Med. 2017, 4, 79. [Google Scholar] [CrossRef] [Scilit]
- Kwatra, G.; Cunnington, M.C.; Merrall, E.; Adrian, P.V.; Ip, M.; Klugman, K.P.; Tam, W.H.; Madhi, S.A. Prevalence of Maternal Colonisation with Group B Streptococcus: A Systematic Review and Meta-Analysis. Lancet Infect. Dis. 2016, 16, 1076–1084. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ding, Y.; Wang, Y.; Hsia, Y.; Russell, N.; Heath, P.T. Systematic Review and Meta-Analyses of Incidence for Group B Streptococcus Disease in Infants and Antimicrobial Resistance, China. Emerg. Infect. Dis. 2020, 26, 2651–2659. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Madrid, L.; Seale, A.C.; Kohli-Lynch, M.; Edmond, K.M.; Lawn, J.E.; Heath, P.T.; Madhi, S.A.; Baker, C.J.; Bartlett, L.; Cutland, C.; et al. Infant Group B Streptococcal Disease Incidence and Serotypes Worldwide: Systematic Review and Meta-Analyses. Clin. Infect. Dis. 2017, 65, S160–S172. [Google Scholar] [CrossRef] [Scilit]
- Were, L.M.; Otieno, J.A.; Miheso, B.; Mayieka, L.M.; Alobo, M.; Caleb, S.K.; Ochodo, E. Group B Streptococcus in Pregnant Women and Neonates in Africa: A Scoping Review. BMJ Public Health 2025, 3, e002263. [Google Scholar] [CrossRef] [Scilit]
- Medugu, N.; Iregbu, K.; Iroh Tam, P.-Y.; Obaro, S. Aetiology of Neonatal Sepsis in Nigeria, and Relevance of Group B Streptococcus: A Systematic Review. PLoS ONE 2018, 13, e0200350. [Google Scholar] [CrossRef] [Scilit]
- Sahuquillo-Arce, J.M.; Hernández-Cabezas, A.; Castaño-Aroca, M.J.; Chouman-Arcas, R.; Díaz-Aguirre, E.; Acosta-Boga, B.; López-Hontangas, J.L. Streptococcus agalactiae in Childbearing Age Immigrant Women in Comunitat Valenciana (Spain). Sci. Rep. 2020, 10, 9904. [Google Scholar] [CrossRef] [Scilit]
- Tsolia, M.; Psoma, M.; Gavrili, S.; Petrochilou, V.; Michalas, S.; Legakis, N.; Karpathios, T. Group B Streptococcus Colonization of Greek Pregnant Women and Neonates: Prevalence, Risk Factors and Serotypes. Clin. Microbiol. Infect. 2003, 9, 832–838. [Google Scholar] [CrossRef] [Scilit]
- Mavenyengwa, R.T.; Moyo, S.R.; Nordbø, S.A. Streptococcus agalactiae Colonization and Correlation with HIV-1 and HBV Seroprevalence in Pregnant Women from Zimbabwe. Eur. J. Obstet. Gynecol. Reprod. Biol. 2010, 150, 34–38. [Google Scholar] [CrossRef] [Scilit]
- Ngayomela, P.H.; Kiritta, R.; Remi, B.A.; Mboya, S.T.; Moremi, N.; Matovelo, D.; Mujuni, F.; Mshana, S.E.; Daubenberger, C.; Zadoks, R.N.; et al. Streptococcus agalactiae Colonization Is Common among Pregnant Women with HIV Infection and Is Neither Predicted by Hospital Tier nor Trimester in Mwanza, Tanzania. BMC Pregnancy Childbirth 2025, 25, 478. [Google Scholar] [CrossRef] [Scilit]
- Dauby, N.; Adler, C.; Miendje Deyi, V.Y.; Sacheli, R.; Busson, L.; Chamekh, M.; Marchant, A.; Barlow, P.; De Wit, S.; Levy, J.; et al. Prevalence, Risk Factors, and Serotype Distribution of Group B Streptococcus Colonization in HIV-Infected Pregnant Women Living in Belgium: A Prospective Cohort Study. Open Forum Infect. Dis. 2018, 5, ofy320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gray, K.J.; Kafulafula, G.; Matemba, M.; Kamdolozi, M.; Membe, G.; French, N. Group B Streptococcus and HIV Infection in Pregnant Women, Malawi, 2008–2010. Emerg. Infect. Dis. 2011, 17, 1932–1935. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- El Beitune, P.; Duarte, G.; Maffei, C.M.L.; Quintana, S.M.; De Sá Rosa E Silva, A.C.J.; Nogueira, A.A. Group B Streptococcus Carriers among HIV-1 Infected Pregnant Women: Prevalence and Risk Factors. Eur. J. Obstet. Gynecol. Reprod. Biol. 2006, 128, 54–58. [Google Scholar] [CrossRef] [Scilit]
- Morgan, J.A.; Hankins, M.E.; Callais, N.A.; Albritton, C.W.; Vanchiere, J.A.; Betcher, R.E.; Lewis, D.F. Group B Streptococcus Rectovaginal Colonization and Resistance Patterns in HIV-Positive Compared to HIV-Negative Pregnant Patients. Am. J. Perinatol. 2023, 40, 1573–1578. [Google Scholar] [CrossRef] [Scilit]
- Van Kassel, M.N.; Janssen, S.W.C.M.; Kofman, S.; Brouwer, M.C.; Van De Beek, D.; Bijlsma, M.W. Prevalence of Group B Streptococcal Colonization in the Healthy Non-Pregnant Population: A Systematic Review and Meta-Analysis. Clin. Microbiol. Infect. 2021, 27, 968–980. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barkham, T.; Sheppard, A.; Jones, N.; Chen, S.L. Streptococcus agalactiae That Caused Meningitis in Healthy Adults in 1998 Are ST283, the Same Type That Caused a Food-Borne Outbreak of Invasive Sepsis in 2015: An Observational Molecular Epidemiology Study. Clin. Microbiol. Infect. 2018, 24, 923–925. [Google Scholar] [CrossRef] [Scilit]
- Muthanna, A.; Desa, M.N.M.; Rahman, N.A.A.; Dzaraly, N.D.; Baharin, N.H.Z.; Aziz, N.A.; Shan, C.H.; Ismail, Z.; Nor, L.A.M.; Ali, M.M.; et al. Epidemiological Observations of Invasive Group B Streptococcus Infections in Six Major Hospitals in Peninsular Malaysia. Asian Pac. J. Trop. Med. 2024, 17, 384–391. [Google Scholar] [CrossRef] [Scilit]
- Luiz, F.B.D.O.; Alves, K.B.; Barros, R.R. Prevalence and Long-Term Persistence of Beta-Haemolytic Streptococci Throat Carriage among Children and Young Adults. J. Med. Microbiol. 2019, 68, 1526–1533. [Google Scholar] [CrossRef] [Scilit]
- Navaneeth, B.V.; Nimananda, R.; Chawda, S.; Selvarani, P.; Bhaskar, M.; Suganthi, N. Prevalence of Beta Hemolytic Streptococci Carrier Rate among Schoolchildren in Salem. Indian J. Pediatr. 2001, 68, 985–986. [Google Scholar] [CrossRef] [Scilit]
- Ghiasi, M.; Fazaeli, H.; Kalhor, N.; Sheykh-Hasan, M.; Tabatabaei-Qomi, R. Assessing the Prevalence of Bacterial Vaginosis among Infertile Women of Qom City. Iran. J. Microbiol. 2014, 6, 404–408. [Google Scholar]
- Manning, S.D.; Tallman, P.; Baker, C.J.; Gillespie, B.; Marrs, C.F.; Foxman, B. Determinants of Co-Colonization with Group B Streptococcus among Heterosexual College Couples. Epidemiol. Camb. Mass 2002, 13, 533–539. [Google Scholar] [CrossRef] [Scilit]
- Swain, B.; Rakshit, A.; Sahu, K.K.; Sahoo, N.; Otta, S. Group B Streptococcus: An Unusual Cause for Urinary Tract Infection. J. Clin. Diagn. Res. JCDR 2017, 11, DL05–DL06. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baldan, R.; Droz, S.; Casanova, C.; Knabben, L.; Huang, D.J.; Brülisauer, C.; Kind, A.B.; Krause, E.; Mauerer, S.; Spellerberg, B.; et al. Group B Streptococcal Colonization in Elderly Women. BMC Infect. Dis. 2021, 21, 408. [Google Scholar] [CrossRef] [Scilit]
- Martins, E.R.; Nascimento Do Ó, D.; Marques Costa, A.L.; Melo-Cristino, J.; Ramirez, M. Characteristics of Streptococcus agalactiae Colonizing Nonpregnant Adults Support the Opportunistic Nature of Invasive Infections. Microbiol. Spectr. 2022, 10, e01082-22. [Google Scholar] [CrossRef] [Scilit]
- Neves, F.P.G.; Marlow, M.A.; Rezende-Pereira, G.; Pinheiro, M.G.; Dos Santos, A.F.M.; De Fátima Nogueira De Freitas, M.; Barros, R.R.; Aguiar-Alves, F.; Cardoso, C.A.A.; Riley, L.W. Differences in Gram-Positive Bacterial Colonization and Antimicrobial Resistance among Children in a High Income Inequality Setting. BMC Infect. Dis. 2019, 19, 478. [Google Scholar] [CrossRef] [Scilit]
- Seale, A.C.; Koech, A.C.; Sheppard, A.E.; Barsosio, H.C.; Langat, J.; Anyango, E.; Mwakio, S.; Mwarumba, S.; Morpeth, S.C.; Anampiu, K.; et al. Maternal Colonization with Streptococcus agalactiae and Associated Stillbirth and Neonatal Disease in Coastal Kenya. Nat. Microbiol. 2016, 1, 16067. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brochet, M.; Couvé, E.; Bercion, R.; Sire, J.-M.; Glaser, P. Population Structure of Human Isolates of Streptococcus agalactiae from Dakar and Bangui. J. Clin. Microbiol. 2009, 47, 800–803. [Google Scholar] [CrossRef] [Scilit]
- Tulyaprawat, O.; Pharkjaksu, S.; Shrestha, R.K.; Ngamskulrungroj, P. Emergence of Multi-Drug Resistance and Its Association with Uncommon Serotypes of Streptococcus agalactiae Isolated from Non-Neonatal Patients in Thailand. Front. Microbiol. 2021, 12, 719353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muthanna, A.; Desa, M.N.M.; Alsalemi, W.; Liyana Abd Aziz, N.A.; Dzaraly, N.D.; Baharin, N.H.Z.; Aziz, N.A.; Ali, M.M.; Nor, L.A.M.; Ismail, Z.; et al. Phenotypic and Genotypic Comparison of Pathogenic Group B Streptococcus Isolated from Human and Cultured Tilapia (Oreochromis Species) in Malaysia. Comp. Immunol. Microbiol. Infect. Dis. 2023, 97, 101993. [Google Scholar] [CrossRef] [Scilit]
- Teatero, S.; Ferrieri, P.; Martin, I.; Demczuk, W.; McGeer, A.; Fittipaldi, N. Serotype Distribution, Population Structure, and Antimicrobial Resistance of Group B Streptococcus Strains Recovered from Colonized Pregnant Women. J. Clin. Microbiol. 2017, 55, 412–422. [Google Scholar] [CrossRef] [Scilit]
- Creti, R.; Imperi, M.; Berardi, A.; Lindh, E.; Alfarone, G.; Pataracchia, M.; Recchia, S. The Italian Network on Neonatal and Infant GBS Infections. Invasive Group B Streptococcal Disease in Neonates and Infants, Italy, Years 2015–2019. Microorganisms 2021, 9, 2579. [Google Scholar] [CrossRef] [Scilit]
- Lawn, J.E.; Chandna, J.; Paul, P.; Jit, M.; Trotter, C.; Lambach, P.; Ter-Meulen, A.S. Every Country, Every Family: Time to Act for Group B Streptococcal Disease Worldwide. Clin. Infect. Dis. Off. Publ. Infect. Dis. Soc. Am. 2022, 74, S1–S4. [Google Scholar] [CrossRef] [Scilit]
- Onile, B.A. Group B Streptococcal Neonatal and Infant Infections in Nigeria: A Review and Update. East Afr. Med. J. 1984, 61, 591–595. [Google Scholar] [PubMed]
- Danmallam, F.A.; Pimenov, N.V. Study on Prevalence, Clinical Presentation, and Associated Bacterial Pathogens of Goat Mastitis in Bauchi, Plateau, and Edo States, Nigeria. Vet. World 2019, 12, 638–645. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Airede, K.I.; Adeyemi, O.; Ibrahim, T. Neonatal Bacterial Meningitis and Dexamethasone Adjunctive Usage in Nigeria. Niger. J. Clin. Pract. 2008, 11, 235–245. [Google Scholar]
- Ako-Nai, K. The Bacteriology of Neonatal Septicaemia in Ile-Ife, Nigeria. J. Trop. Pediatr. 1999, 45, 146–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obadare, T.O.; Adejuyigbe, E.A.; Adeyemo, A.T.; Amupitan, A.A.; Ugowe, O.J.; Anyabolu, C.H.; Aboderin, A.O. Clinical and Bacteriological Profiles of Neonatal Sepsis in a Tertiary Hospital, South-Western Nigeria. Germs 2023, 13, 137. [Google Scholar] [CrossRef] [Scilit]
- Airede, A.I. Neonatal Bacterial Meningitis in the Middle Belt of Nigeria. Dev. Med. Child Neurol. 1993, 35, 424–430. [Google Scholar] [CrossRef] [Scilit]
- Longe, A.C.; Omene, J.A.; Okolo, A.A. Neonatal Meningitis in Nigerian Infants. Acta Paediatr. 1984, 73, 477–481. [Google Scholar] [CrossRef] [Scilit]
- Lawal, S.F.; Odugbemi, T. Antibiogram of Lagos Strains of Beta-Haemolytic Streptococci. J. Chemother. 1989, 1, 285–286. [Google Scholar]
- Nwachukwu, I. Antibacterial Resistance Patterns of Group B Streptococcus Infections in Pregnant Women Attending St John’s Hospital, Owerri, Nigeria. Multidiscip. Res. Dev. J. Int’l 2024, 5, 1–7. [Google Scholar]
- Nwankwu, E.O.; Njoku-Obi, A.N. Serogroups of Beta-Haemolytic Streptococci Isolated from Clinical Specimens in Parts of Eastern Nigeria. J. Commun. Dis. 1990, 22, 269–273. [Google Scholar]
- Omololu-Aso, J. Group B Streptococcus in Pregnancy and Neonatal Colonization at Primary Health Care Institution Nigeria. Am. J. Trop. Med. Hyg. 2018, 99, 164. [Google Scholar]
- Nwadioha, S.I.; Nwokedi, E.O.P.; Onwuezube, I.; Egesie, J.O.; Kashibu, E. Bacterial Isolates from Cerebrospinal Fluid of Children with Suspected Acute Meningitis in a Nigerian Tertiary Hospital. Niger. Postgrad. Med. J. 2013, 20, 9–13. [Google Scholar] [CrossRef] [Scilit]
- Onile, B.A. Group B Streptoccoccal Carriage in Nigeria. Trans. R. Soc. Trop. Med. Hyg. 1980, 74, 367–370. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Onile, B.A.; Osinusi, B.O.; Montefiore, D.; Sogbetun, A.O. Neonatal Septicemia Resulting from Group B Streptococci: A Case Report. Int. J. Gynecol. Obstet. 1980, 17, 393–395. [Google Scholar] [CrossRef] [Scilit]
- Manning, S.D. Correlates of Antibiotic-Resistant Group B Streptococcus Isolated from Pregnant Women. Obstet. Gynecol. 2003, 101, 74–79. [Google Scholar] [CrossRef] [Scilit]
- Mueller, M.; Henle, A.; Droz, S.; Kind, A.B.; Rohner, S.; Baumann, M.; Surbek, D. Intrapartum Detection of Group B Streptococci Colonization by Rapid PCR-Test on Labor Ward. Eur. J. Obstet. Gynecol. Reprod. Biol. 2014, 176, 137–141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elikwu, C.J.; Oduyebo, O.; König, B. Antibiotic Susceptibility Profiles of Group B Streptococci (GBS) Isolates from Pregnant Mothers in a Tertiary Institution in Nigeria. Int. J. Infect. Dis. 2014, 21, 348. [Google Scholar] [CrossRef] [Scilit]
- Omololu-Aso, J.; Omololu-Aso, O.O.; Akinlolu, J.T.; Grace, A.B.; Tunde, A.M. A Case Study of Group B Streptococcus Associated with Women in Antepartum Period and Their Neonates, Ile Ife South-Western Nigeria. Arch. Clin. Microbiol. 2017, 8, 68. [Google Scholar]
- Adewumi, O. Microbiological Pattern in Preterm Prelabour Rupture of the Fetal Membranes in South-Western Nigeria. Obstet. Gynecol. Int. J. 2017, 6, 101–105. [Google Scholar] [CrossRef] [Scilit]
- Onalo, R.; Adeleke, S.I.; Nwalorzie, C.; Njoku, R. Rate of Isolation of Streptococcus Species from Children with Bacterial Infections: An Indication for Introduction of Streptococcal Vaccines. Niger. J. Paediatr. 2011, 38, 136–141. [Google Scholar] [CrossRef] [Scilit]
- Le Bris, J.E.; Pell, M.E.; Medugu, N.; Manning, S.D. Investigating Group B Streptococcus (GBS) Genetic Factors Associated with Vertical Transmission and Invasive Neonatal Disease in Nigeria. Spartan Med. Res. J. 2024, 9, 91. [Google Scholar] [CrossRef] [Scilit]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.