


Abstract
Cholestasis encompasses a broad spectrum of hepatobiliary disorders characterized by impaired bile formation or flow. Historically classified based on clinical onset and severity, the landscape of cholestatic liver disease has been revolutionized by the advent of high-throughput genomic technologies. This review elucidates the critical role of genetics in redefining the pathophysiology, diagnosis, and management of cholestasis, framing pediatric Progressive Familial Intrahepatic Cholestasis (PFIC) and Adult-Onset Cholestatic Disease (AOCD) as a continuous phenotypic spectrum. We discuss the expansion of the molecular nosology to include 13 distinct PFIC types, highlighting how defects in canalicular transporters, tight junctions, and nuclear receptors underpin clinical heterogeneity. Furthermore, we examine the paradigm shift in the diagnostic flowchart, where Next-Generation Sequencing (NGS) has largely superseded liver biopsy for etiological definition. Finally, we address the therapeutic implications of this molecular precision, demonstrating how specific genotypes dictate eligibility for novel targeted therapies, such as IBAT inhibitors, marking the transition from supportive care to personalized medicine.
1. Introduction: Pathophysiology and Clinical Spectrum
The term cholestasis derives from the Greek cholé (bile) and stasis (stagnation) and describes a pathophysiological state characterized by impaired bile formation and/or flow, resulting in the retention of potentially toxic bile acids and other biliary components within the liver and systemic circulation. At the cellular level, retained hydrophobic bile acids exert direct hepatotoxicity through multiple mechanisms, including impairment of mitochondrial electron transport chain (ETC) complexes, disruption of mitochondrial dynamics (fission/fusion balance), and induction of oxidative stress via the mitochondrial permeability transition pore, ultimately promoting hepatocyte apoptosis and inflammatory signaling [1,2]. Cholestasis is classified as intrahepatic or extrahepatic depending on the site of impairment and is defined as chronic when symptoms persist for more than six months [3].
Chronic cholestatic conditions are predominantly intrahepatic in origin, arising from hepatocellular functional defects (functional cholestasis) or lesions affecting the microscopic intrahepatic biliary tree. Conversely, extrahepatic (or obstructive) cholestasis is caused by mechanical obstruction of the large bile ducts outside the liver, such as in sclerosing cholangitis or biliary lithiasis [3,4].
Patients present with a wide spectrum of clinical signs, among which pruritus, jaundice, fatigue, acholic stools, dark urine, and malabsorption of dietary lipids and fat-soluble vitamins represent the most distinctive features. The etiology of cholestasis is diverse, encompassing viral hepatitis, total parenteral nutrition (TPN)-associated cholestasis, drug-induced liver injury (DILI), mechanical obstructions (e.g., gallstones, tumors), and genetic disorders. Among these, genetic defects provide a unique molecular window into the fundamental mechanisms of bile formation and enterohepatic circulation and serve as the primary focus of this review [3,5].
Cholestatic disorders affect both pediatric and adult populations, displaying a phenotypic continuum with distinct clinical trajectories (Figure 1). While pediatric forms typically manifest with severe, chronic presentations, adult-onset phenotypes are generally milder and frequently intermittent and transient. However, the genetic underpinnings of these conditions often overlap, establishing significant pathophysiological links between pediatric and adult cholestatic phenotypes [6,7,8].
Figure 1.
The phenotypic continuum of Familial Intrahepatic Cholestasis (FIC). This diagram illustrates the paradigm shift from a rigid, age-based classification to a unified molecular spectrum. (Left) Pediatric Progressive Familial Intrahepatic Cholestasis (PFIC) represents the severe, early-onset end of the spectrum, typically driven by high-penetrance biallelic mutations and progressing to terminal liver failure. (Right) Adult-Onset Cholestatic Disease (AOCD) occupies the milder end, characterized by variable or transient phenotypes such as Intrahepatic Cholestasis of Pregnancy (ICP), Benign Recurrent Intrahepatic Cholestasis (BRIC), and Drug-Induced Cholestasis (DIC), often associated with heterozygous variants and environmental triggers. The arrows highlight the shared genetic basis, demonstrating that the same key transporter genes (ABCB11, ATP8B1, ABCB4) underpin the entire spectrum, with clinical severity determined by the specific mutational burden and complexity.
2. The Genetic Basis of Pediatric Cholestasis
Among hereditary cholestatic conditions, Progressive Familial Intrahepatic Cholestasis (PFIC) constitutes the most well-defined group. It is characterized by pediatric onset and a severe phenotype—including jaundice, intractable pruritus, hepatosplenomegaly, and growth failure due to malabsorption—often progressing to liver failure. Clinical symptoms typically arise in the neonatal period or within the first year of life, advancing to end-stage liver disease (ESLD) between infancy and adolescence. Ultimately, the condition requires liver transplantation or leads to death, depending on the severity of the presentation [9,10].
PFIC encompasses a spectrum of distinct disorders following an autosomal recessive inheritance pattern. Historically, the nosology was anchored to clinical phenotype and biochemical features. The advent of high-throughput sequencing has redefined this landscape. Currently, OMIM recognizes 13 distinct types of PFIC, each driven by mutations in a specific gene [8]. This genetic heterogeneity reflects a broader pathophysiological reality: cholestasis can arise not only from direct pump failure but also from defects in tight junction integrity, vesicle trafficking, and nuclear receptor signaling (Figure 2). While the “classical” forms (PFIC1–3) remain the most prevalent, this expanded classification (summarized in Table 1) highlights the intricate complexity of the adaptive signaling pathways governing hepatobiliary homeostasis [11].
Figure 2.
The molecular landscape of the bile canaliculus and pathophysiology of PFIC subtypes. This scheme illustrates the diverse molecular mechanisms underlying cholestasis at the hepatocyte apical membrane. (Left) The “classical” forms involve direct defects in canalicular transporters and membrane dynamics: PFIC2 (ABCB11) results in failed bile acid excretion, PFIC3 (ABCB4) impairs phosphatidylcholine secretion leading to bile salt-induced membrane damage, and PFIC1 (ATP8B1) compromises membrane lipid asymmetry. (Right) Newer subtypes reveal complex non-transporter mechanisms: PFIC4 (TJP2) disrupts tight junction integrity, causing paracellular bile leakage; PFIC5 (NR1H4) represents a nuclear regulatory defect where FXR failure prevents the transcriptional upregulation of ABCB11. Additionally, trafficking defects (e.g., PFIC8, 10, 12) involve motor and fusion proteins (KIF12, MYO5B, VPS33B) that cause the intracellular mislocalization of otherwise functional transporters.
Table 1.
Major molecular, biochemical, and clinical characteristics of the 13 identified PFIC types. This table summarizes the expanded nosology of PFIC, correlating specific gene defects with their corresponding protein functions and clinical phenotypes. It highlights the diagnostic utility of serum gamma-glutamyl transferase (GGT) levels in distinguishing between subtypes—contrasting the “normal/low GGT” signature of PFIC1, 2, 4, 5, 7, 10, 11, and 12 with the elevated levels typical of PFIC3, 6, 8, and 9. The classification reflects the diverse pathophysiology of cholestasis, ranging from primary transporter defects to impairments in tight junctions, intracellular trafficking, and nuclear receptor signaling.
2.1. Classical Transporter Defects (PFIC1, 2, 3)
PFIC2 is the most common subtype, followed by PFIC3, while PFIC1 is relatively rare. These “classical” forms are associated with genes that are also implicated in transient or milder cholestatic conditions in adults, creating a genetic bridge across the age spectrum.
PFIC1 is caused by biallelic mutations affecting the P-type ATPase FIC1, encoded by the ATP8B1 gene (OMIM 211600). FIC1 maintains the asymmetric distribution of phospholipids in the canalicular membrane, thereby protecting the hepatocyte from bile salt-induced damage. This function complements that of MDR3, which protects the biliary epithelium by secreting phosphatidylcholine into bile. Loss-of-function mutations render the membrane vulnerable to bile salt-induced damage [12,13]. Pathogenic variants in ATP8B1 are also associated with milder forms such as Benign Recurrent Intrahepatic Cholestasis-1 (BRIC1) and Intrahepatic Cholestasis of Pregnancy-1 (ICP1) [14].
PFIC2 results from biallelic mutations in the ABCB11 gene (OMIM 601847), encoding the bile salt export pump (BSEP). Mutations lead to defective BSEP expression or function, impairing the excretion of conjugated bile acids. A hallmark feature is the significant intrahepatic retention of bile salts with normal or low serum gamma-glutamyl transferase (GGT) levels, as the low biliary bile acid concentration is insufficient to damage the biliary epithelium and release GGT [3]. ABCB11 mutations are also found in BRIC2 and increase susceptibility to ICP [14].
PFIC3 is caused by biallelic mutations in the ABCB4 gene (OMIM 602347), encoding the MDR3 floppase, which translocates phosphatidylcholine (PC) into bile. Unlike types 1 and 2, PFIC3 is characterized by elevated serum GGT levels, resulting from the detergent effect of free bile salts on cholangiocytes in the absence of protective phospholipids [15]. ABCB4 variants are associated with a broad spectrum of adult phenotypes, including biliary fibrosis, cirrhosis, and ICP [14,16].
Notably, the relevance of ABCB4 deficiency in biliary pathology is further underscored by the Mdr2 (Abcb4) knockout mouse, the murine orthologue of human MDR3/ABCB4, which spontaneously develops biliary fibrosis with features resembling primary sclerosing cholangitis, thus providing a valuable preclinical model for studying the progression from phospholipid secretion failure to sclerosing cholangiopathy [17].
2.2. Defects in Canalicular Integrity and Regulation (PFIC4, 5)
Recent advances have identified PFIC subtypes caused by mechanisms beyond direct transporter failure, involving tight junction integrity and nuclear receptor signaling.
PFIC4 (OMIM 615878) results from biallelic mutations in the TJP2 gene. The encoded protein (TJP2/ZO-2) is crucial for the assembly of tight junctions. The hypothesized mechanism involves the failure of claudin-1 to localize to the bile canaliculi seals, leading to paracellular leakage of bile acids into the liver parenchyma. This creates a specific hepatic microenvironment where constant exposure to bile acids causes severe damage, explaining why the liver is the primary site of pathology despite the protein’s ubiquitous expression [18,19].
PFIC5 (OMIM 617049) is caused by mutations in the NR1H4 gene (encoding FXR), the master transcriptional regulator of bile acid homeostasis. This represents a regulatory defect: the absence of FXR prevents the upregulation of BSEP and other transporters [20]. Clinically, PFIC5 presents with normal GGT and a distinctive early-onset vitamin K-independent coagulopathy, reflecting FXR’s role in regulating coagulation factors [21]. Histology mimics PFIC2 (absent BSEP), but the primary defect is upstream at the transcriptional level [8,22].
2.3. Emerging Subtypes: Intracellular Trafficking and Cell Polarity (PFIC6–13)
The most recent expansion of the PFIC spectrum underscores that a functional transporter is ineffective if it cannot effectively reach the canalicular membrane. This group comprises disorders caused by defects in intracellular trafficking, cell polarity, and structural scaffolding. Genes such as MYO5B (PFIC10) and KIF12 (PFIC8) encode motor proteins, while VPS33B (PFIC12) encodes a Sec1/Munc18-family protein that regulates vesicle fusion. Together, these are essential for the polarization of the hepatocyte and the vesicular transport of apical proteins [23,24,25,26,27]. Mutations in these genes result in the “mislocalization” of BSEP and MDR3, mimicking a primary transporter defect despite the transporter genes themselves being intact. Additionally, this category includes defects in the basolateral export machinery (SLC51A, PFIC6, OMIM 619484) [28,29] and other junctional or signaling components (USP53, PFIC7, OMIM 619658; SEMA7A, PFIC11, ZFYVE19, PFIC9), further illustrating that cholestasis can originate from dysfunction at any step of the bile secretion machinery [30,31,32,33].
3. Adult-Onset Cholestatic Disease (AOCD) and the Clinical Continuum
Adult-Onset Cholestatic Disease (AOCD) encompasses a heterogeneous group of conditions characterized by variable severity, including Benign Recurrent Intrahepatic Cholestasis (BRIC), Intrahepatic Cholestasis of Pregnancy (ICP), Drug-Induced Cholestasis (DIC), and Low-Phospholipid-Associated Cholelithiasis (LPAC). Unlike the Mendelian recessive patterns of pediatric forms, AOCD is often complex, involving heterozygous variants, incomplete penetrance, and environmental triggers.
Benign Recurrent Intrahepatic Cholestasis (BRIC) is characterized by recurrent, self-limiting episodes of jaundice and severe pruritus separated by symptom-free intervals [34]. While it shares genetic etiologies with PFIC (ATP8B1, ABCB11), BRIC can present in both biallelic and monoallelic configurations [3,35,36].
Intrahepatic Cholestasis of Pregnancy (ICP) manifests as reversible cholestasis in the second or third trimester. It represents a paradigm of gene-environment interaction, where the hormonal load of pregnancy unmasks a genetic predisposition (e.g., heterozygous variants in ABCB4, ATP8B1, ABCB11) [14,37,38,39].
Drug-Induced Cholestasis (DIC) highlights the role of pharmacogenetics. About 15–20% of the population are low expressers of ABC transporters [40], creating a susceptibility background. Drugs may inhibit BSEP (e.g., cyclosporine, rifampicin) or MRP2 [41,42,43,44,45,46]. Genetic variants in these transporters significantly increase the risk of Drug-Induced Liver Injury (DILI), transforming an idiosyncratic reaction into a predictable vulnerability [47,48,49,50].
Low-Phospholipid-Associated Cholelithiasis (LPAC) is a genetic disorder caused by ABCB4 variants leading to impaired biliary phospholipid secretion, resulting in highly lithogenic bile and recurrent intrahepatic and gallbladder cholesterol cholelithiasis. LPAC typically presents in young adults (before age 40) and is characterized by recurrence of biliary symptoms after cholecystectomy and intrahepatic hyperechogenic foci on ultrasound. ABCB4 variants are identified in approximately 50% of cases and are mostly heterozygous [51,52,53]. LPAC further expands the spectrum of ABCB4-related adult liver disease, alongside ICP and biliary fibrosis, and its chronic evolution may lead to secondary sclerosing cholangitis, biliary cirrhosis, or, rarely, cholangiocarcinoma [53,54].
The Unified Spectrum
The integration of high-throughput genetics with clinical phenotyping has revolutionized the classification of these disorders. The boundaries between pediatric and adult presentations have become indistinct, framing these conditions as a unified Familial Intrahepatic Cholestasis (FIC) continuum. PFIC subtypes represent the severe, early-onset extreme of this spectrum, while AOCD occupies the milder, variable end. Over the years, it has become evident that the same genes responsible for severe PFIC are frequently associated with adult-onset manifestations [7,35,55]. Consequently, AOCD typically manifests as chronic, manageable conditions or transient cholestatic episodes that resolve without significant sequelae, although in some cases they may progress rapidly to liver fibrosis or malignancy [8].
4. Diagnosis of Cholestasis
The accurate diagnosis of cholestatic liver diseases mandates a comprehensive, multidisciplinary approach integrating clinical evaluation, biochemical analysis, radiological imaging, histological examination, and, increasingly, genetic testing [56] (Figure 3). A detailed patient history serves as the foundation of this process, providing the essential context to guide subsequent investigations [3].
Figure 3.
The evolved diagnostic algorithm for pediatric cholestasis: from histology to molecular precision. This flowchart illustrates the paradigm shift from a biopsy-centered approach to a “genotype-first” strategy in the evaluation of cholestatic infants. The diagnostic pathway begins with the initial clinical suspicion based on presenting symptoms (jaundice, acholic stools, dark urine, pruritus) (Blue), followed by the mandatory and urgent exclusion of biliary atresia (BA) through imaging and, when necessary, surgical exploration (Red). Biochemical profiling serves as the initial phenotypic discriminator (Yellow): serum gamma-glutamyl transferase (GGT) levels act as a “phenotypic compass”, where normal or low GGT directs suspicion toward PFIC types 1, 2, 4, 5, 7, 10, 11, and 12 (or bile acid synthesis defects), while elevated GGT suggests PFIC3, 6, 8, and 9, sclerosing cholangitis, or other obstructive/inflammatory etiologies. Magnetic resonance cholangiopancreatography (MRCP) is indicated when structural or sclerosing cholangiopathy is suspected. Next-Generation Sequencing (NGS) has largely superseded liver biopsy for etiological definition (Green): the strategy prioritizes targeted gene panels as the first-line approach, escalating to Whole Exome/Genome Sequencing (WES/WGS) if initial screening is negative, ultimately leading to a defined etiological diagnosis. Liver biopsy and non-invasive fibrosis assessment by vibration-controlled transient elastography (VCTE) (Gray) are reserved for staging hepatic fibrosis, for cases with inconclusive or discordant genetic results, or when evaluation of tissue damage extent is clinically required. Dashed arrows indicate non-routine, conditional, or complementary diagnostic steps. In this modern framework, liver biopsy is no longer the primary diagnostic tool but a complementary modality to genetic testing.
A tailored diagnostic strategy taking age-specific pathophysiology into account is imperative. In the pediatric population, the primary clinical objective is the rapid exclusion of biliary atresia (BA), which accounts for 25–40% of obstructive jaundice cases in the first three months of life and requires urgent surgical intervention [57]. Once surgical causes are excluded, the differential diagnosis broadens to include a spectrum of metabolic and genetic defects. This includes structural bile duct defects, congenital hormonal deficiencies, immune-mediated liver disorders, drug-induced cholestasis, and specific genetic conditions presenting later in childhood [58].
4.1. Role of ESPGHAN Guidelines in Pediatric Practice
While the European Association for the Study of the Liver (EASL) guidelines provide comprehensive recommendations for the management of cholestatic liver diseases across all age groups [36], the European Society for Pediatric Gastroenterology, Hepatology and Nutrition (ESPGHAN) offers specific guidance tailored to the pediatric population [57,59]. ESPGHAN recommendations emphasize the urgency of diagnostic workup in neonatal cholestasis, the importance of early referral to specialized pediatric hepatology centers, and age-appropriate nutritional interventions. The integration of both EASL and ESPGHAN guidelines ensures optimal care across the entire age spectrum, from neonates to adults transitioning from pediatric services.
4.2. Biochemical Investigations: The Phenotypic Compass
Since hyperbilirubinemia and impaired bile acid flux are clinical hallmarks of cholestasis, current guidelines designate serum markers—including direct bilirubin, aminotransferases (ALT/AST), alkaline phosphatase (ALP), gamma-glutamyl transferase (GGT), and markers of synthetic function (glucose, albumin, coagulative profile)—as the first-line investigation to define etiology and severity [57].
Among these, GGT levels represent a pivotal diagnostic discriminator, specifically guiding the genetic suspicion. While GGT and ALP are typically elevated in most pediatric cholestatic conditions [60], a specific subset of hereditary disorders—namely PFIC types 1, 2, 4, 5, 7, 10, 11, and 12—paradoxically present with normal or low GGT levels relative to the degree of cholestasis [56,61]. Recognizing this “low GGT” signature is crucial for directing subsequent molecular testing.
Regarding diagnostic thresholds, both the EASL and the Chinese Medical Association recommend using cut-offs of 1.5 times the upper limit of normal (ULN) for ALP and 3 times the ULN for GGT [3,62]. Moreover, given that biochemical sensitivity varies and the true diagnostic value of these parameters can be uncertain, these markers should be interpreted within the broader clinical context [56]. Additionally, testing for antinuclear (ANA) and antimitochondrial (AMA) antibodies is recommended to exclude autoimmune etiologies, particularly when an overlap between primary sclerosing cholangitis and autoimmune hepatitis is suspected [3,56].
4.3. Imaging and Histological Evaluation
In conjunction with biochemical screening, non-invasive imaging remains the initial step for both pediatric and adult patients. Abdominal ultrasound is primarily used to rule out extrahepatic obstruction [63], while advanced modalities such as computed tomography (CT) and magnetic resonance cholangiopancreatography (MRCP) aid in further distinguishing intrahepatic from extrahepatic cholestasis [56].
Historically, liver biopsy has been considered the gold standard for the definitive diagnosis of intrahepatic cholestasis in 90–95% of cases [63,64,65]. However, liver biopsy is an invasive procedure carrying inherent risks. Consequently, in the current era of precision medicine, there is a paradigm shift towards prioritizing non-invasive molecular investigations. While histology remains indispensable for staging liver fibrosis or when laboratory results are inconclusive [56], Vibration-Controlled Transient Elastography (VCTE) has emerged as a validated non-invasive tool for the assessment of liver fibrosis, offering a reliable surrogate for histological staging in both pediatric and adult cholestatic populations and reducing the need for repeated biopsies during longitudinal follow-up [66]. The integration of Next-Generation Sequencing (NGS) increasingly allows for an accurate etiological diagnosis without the immediate need for invasive sampling. The two approaches are now complementary: biopsy assesses the extent of damage (staging)—increasingly supported or preceded by VCTE as a non-invasive alternative—while genetics defines the cause (etiology) [36,56,66].
4.4. Role of Genetic Testing
The advent of molecular diagnostics has revolutionized the management of cholestasis. The most recent EASL Clinical Practice Guidelines on genetic cholestatic liver diseases strongly recommend genetic testing for infants and children with unexplained cholestasis, as well as for adults after excluding common causes, particularly in cases with atypical features or resistance to standard therapy [36].
4.4.1. Diagnostic Strategy: From Panels to Whole Exome Sequencing
Genetic investigation is paramount in early-onset disease, where high-penetrance variants often drive the phenotype. While targeted gene panels have traditionally been the first-line approach [67], they present a static limitation: they can only detect what is already known. A significant proportion of patients—including pediatric cases with a clear intrahepatic cholestasis phenotype—remains genetically undiagnosed using standard approaches: in a recent single-center pediatric cohort, WES identified disease-causing variants in only 31% of 166 children with intrahepatic cholestasis, and re-analysis of previously negative data led to additional diagnoses through newly published genes [68,69]. This diagnostic gap strongly suggests the existence of causative genes not yet linked to cholestasis in current databases. Consequently, from a prospective standpoint, Whole Exome Sequencing (WES) and Whole Genome Sequencing (WGS) represent superior diagnostic tools. Unlike restricted panels, WES and WGS offer an unbiased genomic interrogation, essential for identifying novel cholestatic genes in “orphan” cases. Furthermore, advanced NGS pipelines now allow for the detection of Copy Number Variations (CNVs)—such as large deletions or duplications—which are frequently missed by standard sequencing but constitute a relevant fraction of pathogenic alleles in cholestasis. Therefore, in patients testing negative on panels, the escalation to WES/WGS is not merely a second step but a necessary strategy to uncover new disease mechanisms [36].
4.4.2. The Challenge of Interpretation: VUS and Functional Validation
The broad application of WES/WGS introduces a new challenge: the interpretation of Variants of Uncertain Significance (VUS). The existence of a phenotypic continuum complicates the establishment of clear genotype–phenotype correlations. Because the same genes can drive diverse clinical outcomes depending on the specific mutational impact, distinguishing pathogenic drivers from benign bystanders is challenging. While initial classification often relies on computational predictions, these are frequently insufficient for the nuanced defects seen in the cholestatic spectrum.
Consequently, the American College of Medical Genetics and Genomics (ACMG) guidelines emphasize the need for evolving evidence to refine classification. Specifically, the PS3 (Pathogenic Strong) and BS3 (Benign Strong) criteria highlight the decisive value of well-established functional studies [70]. These criteria allow robust experimental data demonstrating a deleterious or neutral effect to carry strong evidentiary weight, which can provide the proof needed to reclassify a VUS. This underscores that accurate diagnosis along the FIC continuum relies not merely on sequencing, but on the rigorous integration of genetic data with clinical phenotyping and functional validation. For patients remaining undiagnosed, EASL guidelines recommend re-analyzing sequencing data every three years to capture novel disease-gene associations or reclassify VUS [36,56,66].
4.4.3. Genotype–Phenotype Correlations and Clinical Prognostication
A notable feature of hereditary cholestatic disorders is the phenotypic variability observed among affected individuals. While intrafamilial variability suggests a role for modifier genes and environmental influences in modulating disease expression [71], recent large-scale multicenter evidence has established that the ABCB11 genotype is the primary driver of clinical outcome in BSEP deficiency.
Data from the NAPPED (NAtural course and Prognosis of PFIC and Effect of biliary Diversion) consortium [72] have validated a risk stratification model classifying patients into three distinct groups: BSEP1 (carrying at least one common mild mutation: p.D482G or E297G) [72,73,74,75,76], BSEP2 (at least one missense variant different from BSEP1), and BSEP3 (biallelic protein-truncating mutations, leading to nonfunctional protein or absent BSEP expression). This classification correlates strictly with Native Liver Survival (NLS), which drops significantly from a median of 20.4 years in BSEP1 to just 3.5 years in BSEP3 patients [72].
Understanding these correlations has immediate clinical implications. Crucially, the genotype predicts not only severity but also therapeutic response: while surgical biliary diversion (SBD) effectively extends native liver survival in BSEP1 and BSEP2 patients, it provides no significant benefit in the BSEP3 group, who also face a markedly higher risk of hepatocellular carcinoma (34% by age 15). Consequently, phenotypic prediction is no longer just an active area of research but a validated clinical tool to guide surgical decision-making and transplant prioritization [72,77].
4.5. Diagnosis of Specific Cholestatic Disorders
Applying these diagnostic principles allows for the precise characterization of specific clinical entities within the cholestatic spectrum
4.5.1. Benign Recurrent Intrahepatic Cholestasis (BRIC)
BRIC represents the milder, non-progressive end of the PFIC-BRIC continuum. It shares allelic etiology with severe forms (PFIC) primarily in genes such as ATP8B1 (BRIC1; OMIM 243300) [78] and ABCB11 (BRIC2; OMIM 605479) [79] but typically involves missense variants that retain some residual protein function [80].
Clinically, the diagnosis has traditionally followed established criteria, including multiple distinct episodes of jaundice, separated by asymptomatic periods lasting a minimum of six months, in addition to the exclusion of both medication-induced or toxin-related cholestasis and biliary tract pathology [81]. A suspicion of BRIC is raised when a first cholestatic episode resolves spontaneously, particularly in the presence of a positive family history. However, differential diagnosis is crucial and, to be definitive, typically requires the documentation of a second symptomatic episode. Essential exclusion criteria during the initial attack include acute or chronic viral hepatitis and drug-induced liver injury. Confirmatory features include the documentation of excess fecal bile acid excretion during asymptomatic intervals and normal liver histology months after the resolution of the attack [82]. Today, molecular analysis can expedite this diagnostic timeline, identifying the specific pathogenic variants and differentiating BRIC from progressive forms without the need to await a recurrent episode.
4.5.2. Intrahepatic Cholestasis of Pregnancy (ICP)
ICP is diagnosed based on pruritus, elevated serum total bile acids and liver enzymes, the exclusion of alternative liver pathologies, and the spontaneous resolution of abnormalities approximately three months postpartum [38]. Clinically, ICP presents with varying severity of transaminase and bile acid elevation, with mild hyperbilirubinemia occurring in approximately 30% of cases [83,84]. From a genetic perspective, ICP is increasingly recognized as a manifestation of underlying genetic susceptibility “unmasked” by the hormonal stress of pregnancy. Heterozygous variants in ABC transporter genes (ABCB4, ABCB11, ATP8B1) and other cholestasis-associated loci significantly predispose women to ICP [14,85]. Identifying these variants is clinically critical not only for maternal management but for familial risk assessment: these variants may be inherited by offspring, potentially placing the child at risk for developing severe PFIC if inherited in a recessive pattern or as complex compound heterozygosity. The hormonal milieu of late pregnancy unmasks this genetic susceptibility through multiple converging mechanisms: 17β-estradiol transcriptionally represses BSEP via ERα-mediated interference with FXR signaling [86,87], while sulfated progesterone metabolites—particularly epiallopregnanolone sulfate—competitively inhibit FXR function, further reducing BSEP expression and bile acid efflux [88,89]. These endocrine mechanisms, reviewed in detail elsewhere [90], reinforce the gene-environment paradigm that characterizes ICP within the broader FIC continuum.
4.5.3. Drug-Induced Cholestasis (DIC)
The diagnosis of DIC is primarily one of exclusion, requiring a meticulous medical history to rule out competing etiologies [91]. A detailed pharmacological anamnesis, covering drugs, herbs, and supplements taken in the preceding 6 months, is mandatory [92]. Diagnostic confidence is strengthened by observing worsening liver injury upon rechallenge and improvement following drug withdrawal [93]. Liver injury is biochemically classified as cholestatic when there is a >2-fold elevation in ALP or when the ALT/ALP ratio is ≤2. While DILI is largely idiosyncratic, the genetic component involves susceptibility factors rather than deterministic mutations (e.g., specific HLA alleles) [50]. Although routine screening for cholestatic gene variants is not currently mandated, research suggests that defects in canalicular transporters may lower the threshold for drug toxicity, highlighting the future potential of pharmacogenomics.
4.5.4. Low-Phospholipid-Associated Cholelithiasis (LPAC)
LPAC syndrome should be suspected when at least two of the following criteria are met: onset of biliary symptoms before age 40, recurrence of biliary symptoms after cholecystectomy, and presence of intrahepatic hyperechogenic foci or microlithiasis on ultrasonography [52,54]. Additional features supporting the diagnosis include a personal history of ICP and a family history of gallstones in first-degree relatives [94]. Imaging—particularly liver ultrasound with color Doppler, CT, and MRCP—plays a central role in detecting intrahepatic stones, while ABCB4 genotyping confirms the diagnosis, although variants are identified in only approximately half of cases [95,96]. Early recognition is critical, as LPAC management differs substantially from common gallstone disease: UDCA therapy [10 mg/kg/day] is effective in preventing stone formation and recurrence, and cholecystectomy alone is often insufficient without concomitant medical treatment [54].
5. Therapeutic Management: From Supportive Care to Precision Medicine
The precise molecular characterization achieved through the diagnostic flowchart described above is the prerequisite for selecting the most appropriate therapeutic strategy. Treatment approaches have evolved from purely symptomatic relief to genotype-guided interventions that target the specific molecular defect.
5.1. PFIC Management
Treatment for PFIC is multimodal. While medical therapy remains the first line for all types, its long-term impact on prognosis is variable.
Nutritional support constitutes a fundamental component of PFIC management. Dietary lipids are mainly provided as medium-chain triglycerides (MCTs), as they do not require bile salts for absorption, thereby improving the overall nutritional condition [3]. Supplementation of both water- and fat-soluble vitamins is generally required to correct deficiencies associated with chronic cholestasis.
The pharmacological approach is increasingly stratified by the patient’s specific genetic profile.
Ursodeoxycholic acid (UDCA), a non-hepatotoxic hydrophilic bile acid that modifies the composition of the endogenous bile acid pool [97], is effective for both pediatric and adult-onset forms [98]. However, response to UDCA is strongly genotype-dependent. Its efficacy relies on efficient hepatocellular uptake mediated by NTCP (SLC10A1) [99], and variations in this gene may influence intracellular bioavailability [100]. Regarding efflux defects, patients with PFIC3 (ABCB4) harboring missense mutations with residual phospholipid secretion typically respond well, whereas those with biallelic truncating mutations (complete absence of MDR3) often fail to respond [101]. A similar genotype-response correlation is observed in PFIC2. Symptomatic pruritus control is achieved with conventional agents, including rifampicin and cholestyramine.
Prior to the advent of IBAT inhibitors, bile acid sequestrants—principally cholestyramine—represented the main pharmacological approach to interrupt the enterohepatic circulation of bile acids for the symptomatic relief of cholestatic pruritus. Cholestyramine is a positively charged non-absorbable anion exchange resin that non-specifically binds bile acids in the intestinal lumen, preventing their reabsorption and promoting fecal excretion [102]. However, cholestyramine carries several significant limitations that are particularly relevant in the context of hereditary cholestasis. First, its mechanism is non-selective: the resin binds not only bile acids but also a wide range of co-administered drugs and nutrients, mandating that all concurrent medications—including UDCA and fat-soluble vitamin supplements—be taken at least one hour before or four to six hours after cholestyramine administration to avoid impaired absorption [103]. This is of particular concern in PFIC patients, who already suffer from malabsorption of fat-soluble vitamins as a direct consequence of cholestasis, and in whom cholestyramine can further compound these deficiencies [104]. Second, palatability is notoriously poor, as the granular powder requires suspension in liquid and produces a gritty, unpleasant oral sensation, leading to very low adherence rates, especially in the pediatric population [105,106]. Third, the evidence base for cholestyramine efficacy in PFIC is limited, relying primarily on historical clinical experience and retrospective data rather than randomized controlled trials [102]. Finally, cholestyramine has low efficacy in severe cholestatic diseases where bile acid secretion into the intestinal lumen is already markedly reduced, which is the case in the majority of severe pediatric cholestatic conditions [107].
In contrast, IBAT inhibitors represent a paradigm shift from non-specific intraluminal binding to targeted pharmacological blockade. By selectively and reversibly inhibiting the ileal bile acid transporter (SLC10A2), these agents achieve a more precise interruption of bile acid reabsorption at the molecular level, with a significantly more favorable drug-interaction profile and improved tolerability compared to bile acid sequestrants [102,108]. Crucially, unlike cholestyramine, IBAT inhibitors have been validated through rigorous Phase 3 randomized, placebo-controlled trials (PEDFIC-1, MARCH-PFIC), establishing an evidence-based therapeutic standard for PFIC [109,110].
IBAT inhibitors represent the first approved pharmacological treatments specifically for PFIC [111]. Odevixibat (Bylvay®) was approved by the EMA and FDA in 2021 [112] for the treatment of cholestatic pruritus in PFIC patients aged ≥3 months. In the PEDFIC-1 trial, odevixibat demonstrated significant reductions in serum bile acids and pruritus scores compared to placebo [109].
Maralixibat (Livmarli®), initially approved for Alagille syndrome [113], has subsequently received approval for PFIC, with the MARCH-PFIC trial demonstrating robust efficacy [110]. Recent indirect treatment comparisons suggest that maralixibat may provide additional clinical benefit compared to odevixibat in terms of the proportion of serum bile acid responders (estimated treatment difference 32.3%), although head-to-head trials are lacking [114].
Both drugs act by blocking bile acid reabsorption in the terminal ileum, thereby interrupting enterohepatic circulation and reducing hepatic bile acid load [108,113] (Figure 4). This mechanism requires that bile acids reach the intestinal lumen. Consequently, patients with severe BSEP deficiency (complete absence of functional BSEP protein due to biallelic truncating mutations in ABCB11) are generally unresponsive, as the primary defect prevents bile acid secretion into bile. In contrast, patients with residual transporter function (missense variants with partial activity) may derive significant benefit [109,115]. Both agents are generally well tolerated, with the most common adverse events being gastrointestinal (diarrhea, abdominal pain), which are expected given the mechanism of action and are typically mild to moderate in severity [110,116]. Emerging data suggest that IBAT inhibitors may also improve event-free survival and potentially alter disease progression, expanding their role beyond symptomatic relief [117]. Other IBAT inhibitors are currently undergoing clinical trials to evaluate their efficacy in other cholestatic conditions affecting adults or are awaiting final approval, including linerixibat for the treatment of cholestatic pruritus in patients with primary biliary cholangitis (PBC) [118], and volixibat for the management of pruritus in PBC (https://clinicaltrials.gov/study/NCT05050136 (accessed on 20 December 2025)), primary sclerosing cholangitis (PSC) (https://clinicaltrials.gov/study/NCT04663308 (accessed on 20 December 2025)) and intrahepatic cholestasis of pregnancy [102,111].
Figure 4.
Mechanism of action of IBAT inhibitors and genotype-dependent efficacy. This diagram illustrates the targeted pharmacological interruption of the enterohepatic circulation. (Top) Ileal bile acid transporter (IBAT) inhibitors (e.g., odevixibat, maralixibat) block the physiological reabsorption of bile acids in the terminal ileum. This blockade promotes fecal excretion, thereby reducing the toxic bile acid load returning to the liver and alleviating pruritus. (Bottom) The efficacy of this approach is strictly genotype-dependent. Because the drug acts in the intestinal lumen, it requires bile acids to be present there. Consequently, patients with residual BSEP function (e.g., missense variants) benefit from treatment as bile acids successfully reach the intestine. In contrast, patients with severe BSEP deficiency (e.g., biallelic truncating mutations in ABCB11, corresponding to BSEP3 genotype) are generally unresponsive because the primary canalicular defect prevents bile acids from entering the biliary tree and reaching the site of drug action.
When medical management fails, surgical intervention is required. Biliary diversion procedures, such as partial biliary diversion (PBD) and ileal bypass, aim to mechanically interrupt the enterohepatic circulation [119,120]. Liver transplantation (LT) remains the definitive therapeutic option for ESLD or refractory pruritus, improving symptoms in 75–100% of patients [121]. Of note, patients progressing to ESLD frequently develop systemic complications beyond hepatic dysfunction, including hepatorenal syndrome—driven by splanchnic vasodilation and renal hypoperfusion—and associated fluid and electrolyte disturbances such as dilutional hyponatremia, hyperkalemia, and refractory ascites, which significantly impact pre-transplant management [122,123]. The choice of LT must consider the genetic defect; for instance, in PFIC1 (ATP8B1 deficiency), extrahepatic manifestations such as diarrhea may persist or worsen post-transplant due to the systemic expression of the gene.
5.2. Management of Specific Conditions
In BRIC, treatment aims to limit the duration of cholestatic episodes. UDCA, rifampicin, and cholestyramine are the mainstays of therapy [124,125,126], while in severe, refractory attacks, invasive procedures such as nasobiliary drainage and albumin dialysis may be considered [127,128].
For ICP, pharmacological treatment primarily relies on UDCA to relieve maternal pruritus and improve liver biochemical profiles. Postpartum follow-up is crucial to confirm the resolution of biochemical abnormalities, validating the diagnosis [38].
In DIC, the cornerstone of management is the immediate withdrawal of the offending agent. Causality assessment is supported by validated scales such as the CIOMS/RUCAM [129] and the RECAM [130].
For LPAC, long-term UDCA therapy (10 mg/kg/day) represents the cornerstone of management, reducing biliary lithogenicity by restoring phospholipid solubilization. Cholecystectomy is indicated for symptomatic gallstones but does not prevent recurrence without concomitant UDCA. Complicated forms (recurrent cholangitis, intrahepatic abscess, massive lithiasis) may require endoscopic, radiological, or surgical intervention [54,131].
6. Conclusions
The classification of cholestatic liver diseases has evolved from a rigid, symptom-based nomenclature to a dynamic, molecularly defined continuum. The delineation of 13 distinct PFIC types and their overlap with adult-onset conditions (AOCD) illustrates that pediatric and adult cholestasis are often different facets of the same genetic reality. This conceptual shift—from phenotype-first to genotype-first classification—has profound implications for both clinical practice and research.
The recognition that cholestasis can arise from defects at multiple levels of the bile secretion machinery—canalicular transport (PFIC1–3), tight junction integrity (PFIC4, PFIC7), nuclear receptor signaling (PFIC5), basolateral export (PFIC6), intracellular trafficking (PFIC8–12), and ciliary function (PFIC13)—underscores the remarkable complexity of hepatobiliary homeostasis. Importantly, this expanded molecular nosology has revealed that identical clinical presentations may harbor distinct genetic etiologies, each with specific prognostic and therapeutic implications.
In this new era, genetics is no longer a confirmatory endpoint but the starting point of clinical management. From the early exclusion of biliary atresia to the selection of candidates for IBAT inhibitors, the specific molecular diagnosis drives decision-making at every step. The validation of genotype-based risk stratification models, such as the BSEP1/BSEP2/BSEP3 classification for ABCB11 deficiency, exemplifies how molecular data can now predict native liver survival, hepatocellular carcinoma risk, and response to surgical biliary diversion with clinically actionable precision. These correlations transform genetic testing from a diagnostic tool into a prognostic instrument that directly informs therapeutic choices.
The advent of IBAT inhibitors represents a watershed moment in the management of hereditary cholestasis. For the first time in this specific disease context, a pharmacological class has been designed to target a defined step in the pathophysiological cascade—the enterohepatic circulation of bile acids—offering a mechanism-based intervention that complements the established, albeit broader, cytoprotective effects of UDCA, which has already demonstrated a disease-modifying impact on the natural history of other chronic cholestatic conditions such as primary biliary cholangitis. However, the efficacy of these agents is itself genotype-dependent: patients with residual transporter function stand to benefit most, while those with complete protein absence may require alternative strategies. This pharmacogenomic dimension reinforces the imperative of precise molecular characterization prior to treatment initiation.
Several challenges remain. The interpretation of Variants of Uncertain Significance (VUS) continues to limit diagnostic yield, particularly along the phenotypic continuum where genotype–phenotype correlations are less defined. The periodic re-analysis of genomic data, as recommended by current guidelines, will be essential to reclassify variants as functional evidence accumulates. Furthermore, the contribution of modifier genes and environmental factors to phenotypic variability warrants systematic investigation.
In parallel with genomic advances, recent developments in tissue-based analytical technologies may offer complementary approaches to address these unresolved challenges. In particular, matrix-assisted laser desorption/ionization mass spectrometry imaging (MALDI-MSI) has emerged as a spatially resolved molecular profiling tool capable of mapping the distribution of bile acids, lipids, proteins, and drug metabolites directly within liver tissue sections [132,133,134,135]. Recent studies have demonstrated the ability of MALDI-MSI to visualize the spatial distribution of bile salt species across hepatic parenchyma in cholestatic conditions, identifying molecular structural markers that distinguish healthy from diseased tissue [132], and to characterize the zonation patterns of bile acid metabolism [134]. Moreover, this technology has shown promise in distinguishing mechanisms of biliary toxicity based on the cellular distribution of compounds within the hepatobiliary system [135]. By bridging classical histopathology with unbiased molecular analysis, MALDI-MSI and related spatial metabolomic approaches could, in the future, provide functional tissue-level evidence to support the interpretation of novel VUS and refine genotype–phenotype correlations [133,136]. Nonetheless, it must be emphasized that liver biopsy remains an invasive procedure carrying inherent risks—particularly in pediatric patients—and that the clinical validation, standardization, and accessibility of MALDI-MSI are still under active investigation. Therefore, while these technologies hold considerable potential to enrich the evolving diagnostic approach when biopsy is clinically indicated, they should be considered as a future complementary layer rather than a justification for expanding the indications for invasive tissue sampling.
Looking ahead, the integration of Next-Generation Sequencing with functional validation and emerging biotechnologies—including gene therapy approaches and novel pharmacological targets—promises to transform these complex, often debilitating disorders into manageable, treatable conditions. International collaborative networks, such as the European Reference Network for Rare Liver Diseases (ERN RARE-LIVER) and multicenter consortia like NAPPED, will be instrumental in generating the large-scale genotype–phenotype data necessary to refine prognostic models and optimize therapeutic algorithms.
In conclusion, hereditary cholestatic liver diseases stand at the forefront of precision medicine in hepatology. The molecular redefinition of this disease spectrum has not only deepened our understanding of bile acid biology but has also delivered tangible clinical benefits: earlier diagnosis, accurate prognosis, and targeted therapy. As the field continues to evolve, maintaining rigorous integration of genetic, functional, and clinical data will be essential to fulfill the promise of personalized care for patients across the entire age spectrum.
Author Contributions
Data curation, I.Z. and M.Z.; writing—original draft preparation, I.Z., M.Z. and A.P.d.; writing—review and editing, I.Z., M.Z. and A.P.d.; supervision, A.P.d. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by the Italian Ministry of Health, through the contribution given to the Institute for Maternal and Child Health IRCCS Burlo Garofolo, Trieste - Italy (RC26/17).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| PFIC | Progressive Familial Intrahepatic Cholestasis |
| AOCD | Adult-Onset Cholestatic Disease |
| NGS | Next-Generation Sequencing |
| IBAT | Ileal bile acid transporter |
| ETC | Electron transport chain |
| TPN | Total parenteral nutrition |
| DILI | Drug-induced liver injury |
| ESLD | End-stage liver disease |
| OMIM | Online Mendelian Inheritance in Man |
| BRIC | Benign Recurrent Intrahepatic Cholestasis |
| ICP | Intrahepatic Cholestasis of Pregnancy |
| BSEP | Bile salt export pump |
| GGT | Gamma-glutamyl transferase |
| PC | Phosphatidylcholine |
| DIC | Drug-Induced Cholestasis |
| LPAC | Low-Phospholipid-Associated Cholelithiasis |
| ABC | ATP-binding cassette |
| FIC | Familial Intrahepatic Cholestasis |
| BA | Biliary atresia |
| MRCP | Magnetic resonance cholangiopancreatography |
| WES | Whole Exome Sequencing |
| WGS | Whole Genome Sequencing |
| VCTE | Vibration-Controlled Transient Elastography |
| EASL | European Association for the Study of the Liver |
| ESPGHAN | European Society for Pediatric Gastroenterology, Hepatology and Nutrition |
| ALT | Alanine aminotransferase |
| AST | Aspartate aminotransferase |
| ALP | Alkaline phosphatase |
| ULN | Upper limit of normal |
| ANA | Antinuclear antibodies |
| AMA | Antimitochondrial antibodies |
| CT | Computed tomography |
| CNV | Copy Number Variation |
| VUS | Variant of Uncertain Significance |
| ACMG | American College of Medical Genetics and Genomics |
| NAPPED | NAtural course and Prognosis of PFIC and Effect of biliary Diversion |
| NLS | Native Liver Survival |
| SBD | Surgical biliary diversion |
| HLA | Human leukocyte antigen |
| UDCA | Ursodeoxycholic acid |
| MCT | Medium-chain triglyceride |
| EMA | European Medicines Agency |
| FDA | Food and Drug Administration |
| PBC | Primary biliary cholangitis |
| PSC | Primary sclerosing cholangitis |
| PBD | Partial biliary diversion |
| LT | Liver transplantation |
| CIOMS | Council for International Organizations of Medical Sciences |
| RUCAM | Roussel Uclaf Causality Assessment Method |
| RECAM | Revised Electronic Causality Assessment Method |
| MALDI-MSI | Matrix-assisted laser desorption/ionization mass spectrometry |
| ERN RARE-LIVER | European Reference Network for Rare Liver Diseases |
References
- Li, X.; Ruan, T.; Wang, S.; Sun, X.; Liu, C.; Peng, Y.; Tao, Y. Mitochondria at the Crossroads of Cholestatic Liver Injury: Targeting Novel Therapeutic Avenues. J. Clin. Transl. Hepatol. 2024, 12, 792–801. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, P.; Yao, L.; Yuan, M.; Wang, Z.; Zhang, Q.; Jiang, Y.; Li, L. Mitochondrial dysfunction: A promising therapeutic target for liver diseases. Genes. Dis. 2023, 11, 101115. [Google Scholar] [CrossRef] [Scilit]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines: Management of cholestatic liver diseases. J. Hepatol. 2009, 51, 237–267. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, K.D.; Sundaram, V.; Ayoub, W.S. Atypical causes of cholestasis. World J. Gastroenterol. 2014, 20, 9418–9426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hilscher, M.B.; Kamath, P.S.; Eaton, J.E. Cholestatic Liver Diseases: A Primer for Generalists and Subspecialists. Mayo Clin. Proc. 2020, 95, 2263–2279. [Google Scholar] [CrossRef] [Scilit]
- Nayagam, J.S.; Foskett, P.; Strautnieks, S.; Agarwal, K.; Miquel, R.; Joshi, D.; Thompson, R.J. Clinical phenotype of adult-onset liver disease in patients with variants in ABCB4, ABCB11, and ATP8B1. Hepatol. Commun. 2022, 6, 2654–2664. [Google Scholar] [CrossRef] [Scilit]
- Vitale, G.; Gitto, S.; Raimondi, F.; Mattiaccio, A.; Mantovani, V.; Vukotic, R.; D’Errico, A.; Seri, M.; Russell, R.B.; Andreone, P. Cryptogenic cholestasis in young and adults: ATP8B1, ABCB11, ABCB4, and TJP2 gene variants analysis by high-throughput sequencing. J. Gastroenterol. 2018, 53, 945–958. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vitale, G.; Sciveres, M.; Mandato, C.; d’Adamo, A.P.; Di Giorgio, A. Genotypes and different clinical variants between children and adults in progressive familial intrahepatic cholestasis: A state-of-the-art review. Orphanet J. Rare Dis. 2025, 20, 80. [Google Scholar] [CrossRef] [Scilit]
- Davit-Spraul, A.; Gonzales, E.; Baussan, C.; Jacquemin, E. Progressive familial intrahepatic cholestasis. Orphanet J. Rare Dis. 2009, 4, 1. [Google Scholar] [CrossRef] [Scilit]
- Srivastava, A. Progressive familial intrahepatic cholestasis. J. Clin. Exp. Hepatol. 2014, 4, 25–36. [Google Scholar] [CrossRef] [Scilit]
- Ibrahim, S.H.; Kamath, B.M.; Loomes, K.M.; Karpen, S.J. Cholestatic liver diseases of genetic etiology: Advances and controversies. Hepatology 2022, 75, 1627–1646. [Google Scholar] [CrossRef] [Scilit]
- Groen, A.; Romero, M.R.; Kunne, C.; Hoosdally, S.J.; Dixon, P.H.; Wooding, C.; Williamson, C.; Seppen, J.; Van der Oever, K.; Mok, K.S.; et al. Complementary functions of the flippase ATP8B1 and the floppase ABCB4 in maintaining canalicular membrane integrity. Gastroenterology 2011, 141, 1927–1937.e374. [Google Scholar] [CrossRef] [Scilit]
- Bull, L.N.; van Eijk, M.J.; Pawlikowska, L.; DeYoung, J.A.; Juijn, J.A.; Liao, M.; Klomp, L.W.; Lomri, N.; Berger, R.; Scharschmidt, B.F.; et al. A gene encoding a P-type ATPase mutated in two forms of hereditary cholestasis. Nat. Genet. 1998, 18, 219–224. [Google Scholar] [CrossRef] [Scilit]
- Dixon, P.H.; Sambrotta, M.; Chambers, J.; Taylor-Harris, P.; Syngelaki, A.; Nicolaides, K.; Knisely, A.S.; Thompson, R.J.; Williamson, C. An expanded role for heterozygous mutations of ABCB4, ABCB11, ATP8B1, ABCC2 and TJP2 in intrahepatic cholestasis of pregnancy. Sci. Rep. 2017, 7, 11823. [Google Scholar] [CrossRef] [Scilit]
- de Vree, J.M.; Jacquemin, E.; Sturm, E.; Cresteil, D.; Bosma, P.J.; Aten, J.; Deleuze, J.F.; Desrochers, M.; Burdelski, M.; Bernard, O.; et al. Mutations in the MDR3 gene cause progressive familial intrahepatic cholestasis. Proc. Natl. Acad. Sci. USA 1998, 95, 282–287. [Google Scholar] [CrossRef] [Scilit]
- Sticova, E.; Jirsa, M. ABCB4 disease: Many faces of one gene deficiency. Ann. Hepatol. 2020, 19, 126–133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mariotti, V.; Cadamuro, M.; Spirli, C.; Fiorotto, R.; Strazzabosco, M.; Fabris, L. Animal models of cholestasis: An update on inflammatory cholangiopathies. Biochim. Biophys. Acta Mol. Basis Dis. 2019, 1865, 954–964. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sambrotta, M.; Thompson, R.J. Mutations in TJP2, encoding zona occludens 2, and liver disease. Tissue Barriers 2015, 3, e1026537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Furuse, M.; Fujita, K.; Hiiragi, T.; Fujimoto, K.; Tsukita, S. Claudin-1 and -2: Novel integral membrane proteins localizing at tight junctions with no sequence similarity to occludin. J. Cell Biol. 1998, 141, 1539–1550. [Google Scholar] [CrossRef] [Scilit]
- Makishima, M.; Okamoto, A.Y.; Repa, J.J.; Tu, H.; Learned, R.M.; Luk, A.; Hull, M.V.; Lustig, K.D.; Mangelsdorf, D.J.; Shan, B. Identification of a nuclear receptor for bile acids. Science 1999, 284, 1362–1365. [Google Scholar] [CrossRef] [Scilit]
- Zhan, L.; Liu, H.X.; Fang, Y.; Kong, B.; He, Y.; Zhong, X.B.; Fang, J.; Wan, Y.J.; Guo, G.L. Genome-wide binding and transcriptome analysis of human farnesoid X receptor in primary human hepatocytes. PLoS ONE 2014, 9, e105930. [Google Scholar] [CrossRef] [Scilit]
- Gomez-Ospina, N.; Potter, C.J.; Xiao, R.; Manickam, K.; Kim, M.S.; Kim, K.H.; Shneider, B.L.; Picarsic, J.L.; Jacobson, T.A.; Zhang, J.; et al. Mutations in the nuclear bile acid receptor FXR cause progressive familial intrahepatic cholestasis. Nat. Commun. 2016, 7, 10713. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Girard, M.; Lacaille, F.; Verkarre, V.; Mategot, R.; Feldmann, G.; Grodet, A.; Sauvat, F.; Irtan, S.; Davit-Spraul, A.; Jacquemin, E.; et al. MYO5B and bile salt export pump contribute to cholestatic liver disorder in microvillous inclusion disease. Hepatology 2014, 60, 301–310. [Google Scholar] [CrossRef] [Scilit]
- Gonzales, E.; Taylor, S.A.; Davit-Spraul, A.; Thébaut, A.; Thomassin, N.; Guettier, C.; Whitington, P.F.; Jacquemin, E. MYO5B mutations cause cholestasis with normal serum gamma-glutamyl transferase activity in children without microvillous inclusion disease. Hepatology 2017, 65, 164–173. [Google Scholar] [CrossRef] [Scilit]
- Qiu, Y.L.; Gong, J.Y.; Feng, J.Y.; Wang, R.X.; Han, J.; Liu, T.; Lu, Y.; Li, L.T.; Zhang, M.H.; Sheps, J.A.; et al. Defects in myosin VB are associated with a spectrum of previously undiagnosed low γ-glutamyltransferase cholestasis. Hepatology 2017, 65, 1655–1669. [Google Scholar] [CrossRef] [Scilit]
- Stalke, A.; Sgodda, M.; Cantz, T.; Skawran, B.; Lainka, E.; Hartleben, B.; Baumann, U.; Pfister, E.D. KIF12 Variants and Disturbed Hepatocyte Polarity in Children with a Phenotypic Spectrum of Cholestatic Liver Disease. J. Pediatr. 2022, 240, 284–291.e9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fu, K.; Wang, C.; Gao, Y.; Fan, S.; Zhang, H.; Sun, J.; Jiang, Y.; Liu, C.; Guan, L.; Liu, J.; et al. Metabolomics and Lipidomics Reveal the Effect of Hepatic Vps33b Deficiency on Bile Acids and Lipids Metabolism. Front. Pharmacol. 2019, 10, 276. [Google Scholar] [CrossRef] [Scilit]
- Ballatori, N.; Christian, W.V.; Lee, J.Y.; Dawson, P.A.; Soroka, C.J.; Boyer, J.L.; Madejczyk, S.; Li, N. OSTalpha-OSTbeta: A major basolateral bile acid and steroid transporter in human intestinal, renal, and biliary epithelia. Hepatology 2005, 42, 1270–1279. [Google Scholar] [CrossRef] [Scilit]
- Dawson, P.A.; Hubbert, M.; Haywood, J.; Craddock, A.L.; Zerangue, N.; Christian, W.V.; Ballatori, N. The heteromeric organic solute transporter alpha-beta, Ostalpha-Ostbeta, is an ileal basolateral bile acid transporter. J. Biol. Chem. 2005, 280, 6960–6968. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; Yang, Y.; Gong, J.Y.; Li, L.T.; Li, J.Q.; Zhang, M.H.; Lu, Y.; Xie, X.B.; Hong, Y.R.; Yu, Z.; et al. Low-GGT intrahepatic cholestasis associated with biallelic USP53 variants: Clinical, histological and ultrastructural characterization. Liver Int. 2020, 40, 1142–1150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pan, Q.; Luo, G.; Qu, J.; Chen, S.; Zhang, X.; Zhao, N.; Ding, J.; Yang, H.; Li, M.; Li, L.; et al. A homozygous R148W mutation in Semaphorin 7A causes progressive familial intrahepatic cholestasis. EMBO Mol. Med. 2021, 13, e14563. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luan, W.; Hao, C.Z.; Li, J.Q.; Wei, Q.; Gong, J.Y.; Qiu, Y.L.; Lu, Y.; Shen, C.H.; Xia, Q.; Xie, X.B.; et al. Biallelic loss-of-function ZFYVE19 mutations are associated with congenital hepatic fibrosis, sclerosing cholangiopathy and high-GGT cholestasis. J. Med. Genet. 2021, 58, 514–525. [Google Scholar] [CrossRef] [Scilit]
- Mandato, C.; Siano, M.A.; Nazzaro, L.; Gelzo, M.; Francalanci, P.; Rizzo, F.; D’Agostino, Y.; Morleo, M.; Brillante, S.; Weisz, A.; et al. A ZFYVE19 gene mutation associated with neonatal cholestasis and cilia dysfunction: Case report with a novel pathogenic variant. Orphanet J. Rare Dis. 2021, 16, 179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oude Elferink, R.P.; Paulusma, C.C.; Groen, A.K. Hepatocanalicular transport defects: Pathophysiologic mechanisms of rare diseases. Gastroenterology 2006, 130, 908–925. [Google Scholar] [CrossRef] [Scilit]
- Alhebbi, H.; Peer-Zada, A.A.; Al-Hussaini, A.A.; Algubaisi, S.; Albassami, A.; AlMasri, N.; Alrusayni, Y.; Alruzug, I.M.; Alharby, E.; Samman, M.A.; et al. New paradigms of USP53 disease: Normal GGT cholestasis, BRIC, cholangiopathy, and responsiveness to rifampicin. J. Hum. Genet. 2021, 66, 151–159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines on genetic cholestatic liver diseases. J. Hepatol. 2024, 81, 303–325. [Google Scholar] [CrossRef] [Scilit]
- Kreek, M.J. Female sex steroids and cholestasis. Semin. Liver Dis. 1987, 7, 8–23. [Google Scholar] [CrossRef] [Scilit]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines on the management of liver diseases in pregnancy. J. Hepatol. 2023, 79, 768–828. [Google Scholar] [CrossRef] [Scilit]
- Meier, Y.; Zodan, T.; Lang, C.; Zimmermann, R.; Kullak-Ublick, G.A.; Meier, P.J.; Stieger, B.; Pauli-Magnus, C. Increased susceptibility for intrahepatic cholestasis of pregnancy and contraceptive-induced cholestasis in carriers of the 1331T>C polymorphism in the bile salt export pump. World J. Gastroenterol. 2008, 14, 38–45. [Google Scholar] [CrossRef] [Scilit]
- Meier, Y.; Pauli-Magnus, C.; Zanger, U.M.; Klein, K.; Schaeffeler, E.; Nussler, A.K.; Nussler, N.; Eichelbaum, M.; Meier, P.J.; Stieger, B. Interindividual variability of canalicular ATP-binding-cassette (ABC)-transporter expression in human liver. Hepatology 2006, 44, 62–74. [Google Scholar] [CrossRef] [Scilit]
- Pauli-Magnus, C.; Stieger, B.; Meier, Y.; Kullak-Ublick, G.A.; Meier, P.J. Enterohepatic transport of bile salts and genetics of cholestasis. J. Hepatol. 2005, 43, 342–357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stieger, B.; Fattinger, K.; Madon, J.; Kullak-Ublick, G.A.; Meier, P.J. Drug- and estrogen-induced cholestasis through inhibition of the hepatocellular bile salt export pump (Bsep) of rat liver. Gastroenterology 2000, 118, 422–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morgan, R.E.; Trauner, M.; van Staden, C.J.; Lee, P.H.; Ramachandran, B.; Eschenberg, M.; Afshari, C.A.; Qualls, C.W., Jr.; Lightfoot-Dunn, R.; Hamadeh, H.K. Interference with bile salt export pump function is a susceptibility factor for human liver injury in drug development. Toxicol. Sci. 2010, 118, 485–500. [Google Scholar] [CrossRef] [Scilit]
- Dawson, S.; Stahl, S.; Paul, N.; Barber, J.; Kenna, J.G. In vitro inhibition of the bile salt export pump correlates with risk of cholestatic drug-induced liver injury in humans. Drug Metab. Dispos. 2012, 40, 130–138. [Google Scholar] [CrossRef] [Scilit]
- Byrne, J.A.; Strautnieks, S.S.; Mieli-Vergani, G.; Higgins, C.F.; Linton, K.J.; Thompson, R.J. The human bile salt export pump: Characterization of substrate specificity and identification of inhibitors. Gastroenterology 2002, 123, 1649–1658. [Google Scholar] [CrossRef] [Scilit]
- Aithal, G.P.; Watkins, P.B.; Andrade, R.J.; Larrey, D.; Molokhia, M.; Takikawa, H.; Hunt, C.M.; Wilke, R.A.; Avigan, M.; Kaplowitz, N.; et al. Case definition and phenotype standardization in drug-induced liver injury. Clin. Pharmacol. Ther. 2011, 89, 806–815. [Google Scholar] [CrossRef] [Scilit]
- Choi, J.H.; Ahn, B.M.; Yi, J.; Lee, J.H.; Lee, J.H.; Nam, S.W.; Chon, C.Y.; Han, K.H.; Ahn, S.H.; Jang, I.J.; et al. MRP2 haplotypes confer differential susceptibility to toxic liver injury. Pharmacogenet Genom. 2007, 17, 403–415. [Google Scholar] [CrossRef] [Scilit]
- Daly, A.K.; Aithal, G.P.; Leathart, J.B.; Swainsbury, R.A.; Dang, T.S.; Day, C.P. Genetic susceptibility to diclofenac-induced hepatotoxicity: Contribution of UGT2B7, CYP2C8, and ABCC2 genotypes. Gastroenterology 2007, 132, 272–281. [Google Scholar] [CrossRef] [Scilit]
- Pauli-Magnus, C.; Meier, P.J. Hepatobiliary transporters and drug-induced cholestasis. Hepatology 2006, 44, 778–787. [Google Scholar] [CrossRef] [Scilit]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines: Drug-induced liver injury. J. Hepatol. 2019, 70, 1222–1261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosmorduc, O.; Hermelin, B.; Poupon, R. MDR3 gene defect in adults with symptomatic intrahepatic and gallbladder cholesterol cholelithiasis. Gastroenterology 2001, 120, 1459–1467. [Google Scholar] [CrossRef] [Scilit]
- Rosmorduc, O.; Hermelin, B.; Boelle, P.Y.; Parc, R.; Taboury, J.; Poupon, R. ABCB4 gene mutation-associated cholelithiasis in adults. Gastroenterology 2003, 125, 452–459. [Google Scholar] [CrossRef] [Scilit]
- Davit-Spraul, A.; Gonzales, E.; Baussan, C.; Jacquemin, E. The spectrum of liver diseases related to ABCB4 gene mutations: Pathophysiology and clinical aspects. Semin. Liver Dis. 2010, 30, 134–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosmorduc, O.; Poupon, R. Low phospholipid associated cholelithiasis: Association with mutation in the MDR3/ABCB4 gene. Orphanet J. Rare Dis. 2007, 2, 29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pasmant, E.; Goussard, P.; Baranes, L.; Laurendeau, I.; Quentin, S.; Ponsot, P.; Consigny, Y.; Farges, O.; Condat, B.; Vidaud, D.; et al. First description of ABCB4 gene deletions in familial low phospholipid-associated cholelithiasis and oral contraceptives-induced cholestasis. Eur. J. Hum. Genet. 2012, 20, 277–282. [Google Scholar] [CrossRef] [Scilit]
- Lu, L.; Chinese Society of Hepatology and Chinese Medical Association. Guidelines for the Management of Cholestatic Liver Diseases. J. Clin. Transl. Hepatol. 2022, 10, 757–769. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fawaz, R.; Baumann, U.; Ekong, U.; Fischler, B.; Hadzic, N.; Mack, C.L.; McLin, V.A.; Molleston, J.P.; Neimark, E.; Ng, V.L.; et al. Guideline for the Evaluation of Cholestatic Jaundice in Infants: Joint Recommendations of the North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition and the European Society for Pediatric Gastroenterology, Hepatology, and Nutrition. J. Pediatr. Gastroenterol. Nutr. 2017, 64, 154–168. [Google Scholar] [CrossRef] [Scilit]
- Ranucci, G.; Della Corte, C.; Alberti, D.; Bondioni, M.P.; Boroni, G.; Calvo, P.L.; Cananzi, M.; Candusso, M.; Clemente, M.G.; D’Antiga, L.; et al. Diagnostic approach to neonatal and infantile cholestasis: A position paper by the SIGENP liver disease working group. Dig. Liver Dis. 2022, 54, 40–53. [Google Scholar] [CrossRef] [Scilit]
- Gottesman, L.E.; Del Vecchio, M.T.; Aronoff, S.C. Etiologies of conjugated hyperbilirubinemia in infancy: A systematic review of 1692 subjects. BMC Pediatr. 2015, 15, 192. [Google Scholar] [CrossRef] [Scilit]
- Lu, F.T.; Wu, J.F.; Hsu, H.Y.; Ni, Y.H.; Chang, M.H.; Chao, C.I.; Chen, H.L. γ-Glutamyl transpeptidase level as a screening marker among diverse etiologies of infantile intrahepatic cholestasis. J. Pediatr. Gastroenterol. Nutr. 2014, 59, 695–701. [Google Scholar] [CrossRef] [Scilit]
- Jansen, P.L.; Müller, M. The molecular genetics of familial intrahepatic cholestasis. Gut 2000, 47, 1–5. [Google Scholar] [CrossRef] [Scilit]
- Chinese Society of Hepatology; Chinese Society of Gastroenterology; Chinese Society of Infectious Diseases of the Chinese Medical Association. Consensus on the diagnosis and treatment of cholestatic liver diseases (2015, China). J. Dig. Dis. 2016, 17, 137–154. [Google Scholar] [CrossRef] [Scilit]
- Balistreri, W.F. Neonatal cholestasis. J. Pediatr. 1985, 106, 171–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russo, P.; Magee, J.C.; Boitnott, J.; Bove, K.E.; Raghunathan, T.; Finegold, M.; Haas, J.; Jaffe, R.; Kim, G.E.; Magid, M.; et al. Design and validation of the biliary atresia research consortium histologic assessment system for cholestasis in infancy. Clin. Gastroenterol. Hepatol. 2011, 9, 357–362.e2. [Google Scholar] [CrossRef] [Scilit]
- Morotti, R.A.; Jain, D. Pediatric Cholestatic Disorders: Approach to Pathologic Diagnosis. Surg. Pathol. Clin. 2013, 6, 205–225. [Google Scholar] [CrossRef] [Scilit]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines on non-invasive tests for evaluation of liver disease severity and prognosis—2021 update. J. Hepatol. 2021, 75, 659–689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Togawa, T.; Sugiura, T.; Ito, K.; Endo, T.; Aoyama, K.; Ohashi, K.; Negishi, Y.; Kudo, T.; Ito, R.; Kikuchi, A.; et al. Molecular Genetic Dissection and Neonatal/Infantile Intrahepatic Cholestasis Using Targeted Next-Generation Sequencing. J. Pediatr. 2016, 171, 171–177.e74. [Google Scholar] [CrossRef] [Scilit]
- Herbst, S.M.; Schirmer, S.; Posovszky, C.; Jochum, F.; Rödl, T.; Schroeder, J.A.; Barth, T.F.; Hehr, U.; Melter, M.; Vermehren, J. Taking the next step forward—Diagnosing inherited infantile cholestatic disorders with next generation sequencing. Mol. Cell. Probes 2015, 29, 291–298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, Y.; Guo, H.; Chen, L.; Cheng, W.; Yan, K.; Zhang, Z.; Li, M.; Jin, Y.; Hu, G.; Wang, C.; et al. Diagnostic yield and novel candidate genes by next generation sequencing in 166 children with intrahepatic cholestasis. Hepatol. Int. 2024, 18, 661–672. [Google Scholar] [CrossRef] [Scilit]
- Brnich, S.E.; Abou Tayoun, A.N.; Couch, F.J.; Cutting, G.R.; Greenblatt, M.S.; Heinen, C.D.; Kanavy, D.M.; Luo, X.; McNulty, S.M.; Starita, L.M.; et al. Recommendations for application of the functional evidence PS3/BS3 criterion using the ACMG/AMP sequence variant interpretation framework. Genome Med. 2019, 12, 3. [Google Scholar] [CrossRef] [Scilit]
- van Mil, S.W.; Houwen, R.H.; Klomp, L.W. Genetics of familial intrahepatic cholestasis syndromes. J. Med. Genet. 2005, 42, 449–463. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Wessel, D.B.E.; Thompson, R.J.; Gonzales, E.; Jankowska, I.; Sokal, E.; Grammatikopoulos, T.; Kadaristiana, A.; Jacquemin, E.; Spraul, A.; Lipiński, P.; et al. Genotype correlates with the natural history of severe bile salt export pump deficiency. J. Hepatol. 2020, 73, 84–93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bull, L.N.; Pawlikowska, L.; Strautnieks, S.; Jankowska, I.; Czubkowski, P.; Dodge, J.L.; Emerick, K.; Wanty, C.; Wali, S.; Blanchard, S.; et al. Outcomes of surgical management of familial intrahepatic cholestasis 1 and bile salt export protein deficiencies. Hepatol. Commun. 2018, 2, 515–528. [Google Scholar] [CrossRef] [Scilit]
- Davit-Spraul, A.; Fabre, M.; Branchereau, S.; Baussan, C.; Gonzales, E.; Stieger, B.; Bernard, O.; Jacquemin, E. ATP8B1 and ABCB11 analysis in 62 children with normal gamma-glutamyl transferase progressive familial intrahepatic cholestasis (PFIC): Phenotypic differences between PFIC1 and PFIC2 and natural history. Hepatology 2010, 51, 1645–1655. [Google Scholar] [CrossRef] [Scilit]
- Hayashi, H.; Takada, T.; Suzuki, H.; Akita, H.; Sugiyama, Y. Two common PFIC2 mutations are associated with the impaired membrane trafficking of BSEP/ABCB11. Hepatology 2005, 41, 916–924. [Google Scholar] [CrossRef] [Scilit]
- Dröge, C.; Bonus, M.; Baumann, U.; Klindt, C.; Lainka, E.; Kathemann, S.; Brinkert, F.; Grabhorn, E.; Pfister, E.D.; Wenning, D.; et al. Sequencing of FIC1, BSEP and MDR3 in a large cohort of patients with cholestasis revealed a high number of different genetic variants. J. Hepatol. 2017, 67, 1253–1264. [Google Scholar] [CrossRef] [Scilit]
- Knisely, A.S.; Strautnieks, S.S.; Meier, Y.; Stieger, B.; Byrne, J.A.; Portmann, B.C.; Bull, L.N.; Pawlikowska, L.; Bilezikçi, B.; Ozçay, F.; et al. Hepatocellular carcinoma in ten children under five years of age with bile salt export pump deficiency. Hepatology 2006, 44, 478–486. [Google Scholar] [CrossRef] [Scilit]
- Folmer, D.E.; van der Mark, V.A.; Ho-Mok, K.S.; Oude Elferink, R.P.; Paulusma, C.C. Differential effects of progressive familial intrahepatic cholestasis type 1 and benign recurrent intrahepatic cholestasis type 1 mutations on canalicular localization of ATP8B1. Hepatology 2009, 50, 1597–1605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Mil, S.W.; van der Woerd, W.L.; van der Brugge, G.; Sturm, E.; Jansen, P.L.; Bull, L.N.; van den Berg, I.E.; Berger, R.; Houwen, R.H.; Klomp, L.W. Benign recurrent intrahepatic cholestasis type 2 is caused by mutations in ABCB11. Gastroenterology 2004, 127, 379–384. [Google Scholar] [CrossRef] [Scilit]
- Kagawa, T.; Watanabe, N.; Mochizuki, K.; Numari, A.; Ikeno, Y.; Itoh, J.; Tanaka, H.; Arias, I.M.; Mine, T. Phenotypic differences in PFIC2 and BRIC2 correlate with protein stability of mutant Bsep and impaired taurocholate secretion in MDCK II cells. Am. J. Physiol. Gastrointest. Liver Physiol. 2008, 294, G58–G67. [Google Scholar] [CrossRef] [Scilit]
- Tygstrup, N.; Jensen, B. Intermittent intrahepatic cholestasis of unknown etiology in five young males from the Faroe Islands. Acta Med. Scand. 1969, 185, 523–530. [Google Scholar] [CrossRef] [Scilit]
- Luketic, V.A.; Shiffman, M.L. Benign recurrent intrahepatic cholestasis. Clin. Liver Dis. 2004, 8, 133–149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reyes, H.; Radrigan, M.E.; Gonzalez, M.C.; Latorre, R.; Ribalta, J.; Segovia, N.; Alvarez, C.; Andresen, M.; Figueroa, D.; Lorca, B. Steatorrhea in patients with intrahepatic cholestasis of pregnancy. Gastroenterology 1987, 93, 584–590. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.D.; Yao, Q.; Peng, B.; Zhang, L.; Ai, Y.; Ying, A.Y.; Liu, X.H.; Liu, S.Y. A clinical analysis of intrahepatic cholestasis of pregnancy in 1241 cases. Zhonghua Gan Zang Bing Za Zhi 2007, 15, 291–293. (In Chinese) [Google Scholar] [PubMed]
- Dixon, P.H.; Wadsworth, C.A.; Chambers, J.; Donnelly, J.; Cooley, S.; Buckley, R.; Mannino, R.; Jarvis, S.; Syngelaki, A.; Geenes, V.; et al. A comprehensive analysis of common genetic variation around six candidate loci for intrahepatic cholestasis of pregnancy. Am. J. Gastroenterol. 2014, 109, 76–84. [Google Scholar] [CrossRef] [Scilit]
- Song, X.; Vasilenko, A.; Chen, Y.; Valanejad, L.; Verma, R.; Yan, B.; Deng, R. Transcriptional dynamics of bile salt export pump during pregnancy: Mechanisms and implications in intrahepatic cholestasis of pregnancy. Hepatology 2014, 60, 1993–2007. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Y.; Vasilenko, A.; Song, X.; Valanejad, L.; Verma, R.; You, S.; Yan, B.; Shiffka, S.; Hargreaves, L.; Nadolny, C.; et al. Estrogen and Estrogen Receptor-α-Mediated Transrepression of Bile Salt Export Pump. Mol. Endocrinol. 2015, 29, 613–626. [Google Scholar] [CrossRef] [Scilit]
- Abu-Hayyeh, S.; Papacleovoulou, G.; Lövgren-Sandblom, A.; Tahir, M.; Oduwole, O.; Jamaludin, N.A.; Ravat, S.; Nikolova, V.; Chambers, J.; Selden, C.; et al. Intrahepatic cholestasis of pregnancy levels of sulfated progesterone metabolites inhibit farnesoid X receptor resulting in a cholestatic phenotype. Hepatology 2013, 57, 716–726. [Google Scholar] [CrossRef] [Scilit]
- Vallejo, M.; Briz, O.; Serrano, M.A.; Monte, M.J.; Marin, J.J. Potential role of trans-inhibition of the bile salt export pump by progesterone metabolites in the etiopathogenesis of intrahepatic cholestasis of pregnancy. J. Hepatol. 2006, 44, 1150–1157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zu, Y.; Yang, J.; Zhang, C.; Liu, D. The Pathological Mechanisms of Estrogen-Induced Cholestasis: Current Perspectives. Front. Pharmacol. 2021, 12, 761255. [Google Scholar] [CrossRef] [Scilit]
- Pinazo-Bandera, J.M.; Toro-Ortiz, J.P.; Andrade, R.J.; García-Cortés, M. Drug-induced cholestasis: Causative agents and challenges in diagnosis and management. Explor. Dig. Dis. 2023, 2, 202–222. [Google Scholar] [CrossRef] [Scilit]
- Chalasani, N.P.; Maddur, H.; Russo, M.W.; Wong, R.J.; Reddy, K.R.; Practice Parameters Committee of the American College of Gastroenterology. ACG Clinical Guideline: Diagnosis and Management of Idiosyncratic Drug-Induced Liver Injury. Am. J. Gastroenterol. 2021, 116, 878–898. [Google Scholar] [CrossRef] [Scilit]
- Fontana, R.J.; Bjornsson, E.S.; Reddy, R.; Andrade, R.J. The Evolving Profile of Idiosyncratic Drug-Induced Liver Injury. Clin. Gastroenterol. Hepatol. 2023, 21, 2088–2099. [Google Scholar] [CrossRef] [Scilit]
- Erlinger, S. Low phospholipid-associated cholestasis and cholelithiasis. Clin. Res. Hepatol. Gastroenterol. 2012, 36, S36–S40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, C.; Condat, B.; Picon-Coste, M.; Chrétien, Y.; Potier, P.; Noblinski, B.; Arrivé, L.; Hauuy, M.P.; Barbu, V.; Maftouh, A.; et al. Low-phospholipid-associated cholelithiasis syndrome: Prevalence, clinical features, and comorbidities. JHEP Rep. 2020, 3, 100201. [Google Scholar] [CrossRef] [Scilit]
- Poupon, R.; Rosmorduc, O.; Boëlle, P.Y.; Chrétien, Y.; Corpechot, C.; Chazouillères, O.; Housset, C.; Barbu, V. Genotype-phenotype relationships in the low-phospholipid-associated cholelithiasis syndrome: A study of 156 consecutive patients. Hepatology 2013, 58, 1105–1110. [Google Scholar] [CrossRef] [Scilit]
- Jacquemin, E.; Hermans, D.; Myara, A.; Habes, D.; Debray, D.; Hadchouel, M.; Sokal, E.M.; Bernard, O. Ursodeoxycholic acid therapy in pediatric patients with progressive familial intrahepatic cholestasis. Hepatology 1997, 25, 519–523. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Paumgartner, G.; Beuers, U. Ursodeoxycholic acid in cholestatic liver disease: Mechanisms of action and therapeutic use revisited. Hepatology 2002, 36, 525–531. [Google Scholar] [CrossRef] [Scilit]
- Maeda, K.; Kambara, M.; Tian, Y.; Hofmann, A.F.; Sugiyama, Y. Uptake of ursodeoxycholate and its conjugates by human hepatocytes: Role of Na(+)-taurocholate cotransporting polypeptide (NTCP), organic anion transporting polypeptide (OATP) 1B1 (OATP-C), and oatp1B3 (OATP8). Mol. Pharm. 2006, 3, 70–77. [Google Scholar] [CrossRef] [Scilit]
- Vaz, F.M.; Paulusma, C.C.; Huidekoper, H.; de Ru, M.; Lim, C.; Koster, J.; Ho-Mok, K.; Bootsma, A.H.; Groen, A.K.; Schaap, F.G.; et al. Sodium taurocholate cotransporting polypeptide (SLC10A1) deficiency: Conjugated hypercholanemia without a clear clinical phenotype. Hepatology 2015, 61, 260–267. [Google Scholar] [CrossRef] [Scilit]
- Jacquemin, E.; De Vree, J.M.; Cresteil, D.; Sokal, E.M.; Sturm, E.; Dumont, M.; Scheffer, G.L.; Paul, M.; Burdelski, M.; Bosma, P.J.; et al. The wide spectrum of multidrug resistance 3 deficiency: From neonatal cholestasis to cirrhosis of adulthood. Gastroenterology 2001, 120, 1448–1458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al-Dury, S.; Marschall, H.U. Ileal Bile Acid Transporter Inhibition for the Treatment of Chronic Constipation, Cholestatic Pruritus, and NASH. Front. Pharmacol. 2018, 9, 931. [Google Scholar] [CrossRef] [Scilit]
- Lent-Schochet, D.; Jialal, I. Antilipemic Agent Bile Acid Sequestrants. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2023. [Google Scholar]
- Jung, J.W.; Park, S.Y.; Kim, H. Drug-Induced Vitamin Deficiency. Ann. Clin. Nutr. Metab. 2022, 14, 20–31. [Google Scholar] [CrossRef] [Scilit]
- Riaz, S.; Patel, P.; John, S. Cholestyramine Resin. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2025. [Google Scholar]
- Jacobson, T.A.; Maki, K.C.; Orringer, C.E.; Jones, P.H.; Kris-Etherton, P.; Sikand, G.; La Forge, R.; Daniels, S.R.; Wilson, D.P.; Morris, P.B.; et al. National Lipid Association Recommendations for Patient-Centered Management of Dyslipidemia: Part 2. J. Clin. Lipidol. 2015, 9, S1–S122.e1. [Google Scholar] [CrossRef] [Scilit]
- Thébaut, A.; Debray, D.; Gonzales, E. An update on the physiopathology and therapeutic management of cholestatic pruritus in children. Clin. Res. Hepatol. Gastroenterol. 2018, 42, 103–109. [Google Scholar] [CrossRef] [Scilit]
- Graffner, H.; Gillberg, P.G.; Rikner, L.; Marschall, H.U. The ileal bile acid transporter inhibitor A4250 decreases serum bile acids by interrupting the enterohepatic circulation. Aliment. Pharmacol. Ther. 2016, 43, 303–310. [Google Scholar] [CrossRef] [Scilit]
- Thompson, R.J.; Arnell, H.; Artan, R.; Baumann, U.; Calvo, P.L.; Czubkowski, P.; Dalgic, B.; D’Antiga, L.; Durmaz, Ö.; Fischler, B.; et al. Odevixibat treatment in progressive familial intrahepatic cholestasis: A randomised, placebo-controlled, phase 3 trial. Lancet Gastroenterol. Hepatol. 2022, 7, 830–842. [Google Scholar] [CrossRef] [Scilit]
- Miethke, A.G.; Moukarzel, A.; Porta, G.; Covarrubias Esquer, J.; Czubkowski, P.; Ordonez, F.; Mosca, A.; Aqul, A.A.; Squires, R.H.; Sokal, E.; et al. Maralixibat in progressive familial intrahepatic cholestasis (MARCH-PFIC): A multicentre, randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Gastroenterol. Hepatol. 2024, 9, 620–631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jeyaraj, R.; Maher, E.R.; Kelly, D. Paediatric research sets new standards for therapy in paediatric and adult cholestasis. Lancet Child. Adolesc. Health 2024, 8, 75–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deeks, E.D. Odevixibat: First Approval. Drugs 2021, 81, 1781–1786. [Google Scholar] [CrossRef] [Scilit]
- Shirley, M. Maralixibat: First Approval. Drugs 2022, 82, 71–76. [Google Scholar] [CrossRef] [Scilit]
- Lacey, G.; Gosden, T.; Darlington, O.; Evers, E.; Howard, R.; Quadrado, L. Indirect Comparison of Maralixibat and Odevixibat for the Treatment of Progressive Familial Intrahepatic Cholestasis. Clin. Ther. 2025, 47, 1016–1023. [Google Scholar] [CrossRef] [Scilit]
- Felzen, A.; van Wessel, D.B.E.; Gonzales, E.; Thompson, R.J.; Jankowska, I.; Shneider, B.L.; Sokal, E.; Grammatikopoulos, T.; Kadaristiana, A.; Jacquemin, E.; et al. Genotype-phenotype relationships of truncating mutations, p.E297G and p.D482G in bile salt export pump deficiency. JHEP Rep. 2022, 5, 100626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thompson, R.J.; Artan, R.; Baumann, U.; Calvo, P.L.; Czubkowski, P.; Dalgic, B.; D’Antiga, L.; Di Giorgio, A.; Durmaz, Ö.; Gonzalès, E.; et al. Interim results from an ongoing, open-label, single-arm trial of odevixibat in progressive familial intrahepatic cholestasis. JHEP Rep. 2023, 5, 100782. [Google Scholar] [CrossRef] [Scilit]
- Hansen, B.E.; Vandriel, S.M.; Vig, P.; Garner, W.; Mogul, D.B.; Loomes, K.M.; Piccoli, D.A.; Rand, E.B.; Jankowska, I.; Czubkowski, P.; et al. Event-free survival of maralixibat-treated patients with Alagille syndrome compared to a real-world cohort from GALA. Hepatology 2024, 79, 1279–1292. [Google Scholar] [CrossRef] [Scilit]
- Hirschfield, G.M.; Bowlus, C.L.; Jones, D.E.J.; Kremer, A.E.; Mayo, M.J.; Tanaka, A.; Andreone, P.; Jia, J.; Jin, Q.; Macías-Rodríguez, R.U.; et al. Linerixibat in patients with primary biliary cholangitis and cholestatic pruritus (GLISTEN): A randomised, multicentre, double-blind, placebo-controlled, phase 3 trial. Lancet Gastroenterol. Hepatol. 2026, 11, 22–33. [Google Scholar] [CrossRef] [Scilit]
- Whitington, P.F.; Whitington, G.L. Partial external diversion of bile for the treatment of intractable pruritus associated with intrahepatic cholestasis. Gastroenterology 1988, 95, 130–136. [Google Scholar] [CrossRef] [Scilit]
- Kaliciński, P.J.; Ismail, H.; Jankowska, I.; Kamiński, A.; Pawłowska, J.; Drewniak, T.; Markiewicz, M.; Szymczak, M. Surgical treatment of progressive familial intrahepatic cholestasis: Comparison of partial external biliary diversion and ileal bypass. Eur. J. Pediatr. Surg. 2003, 13, 307–311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aydogdu, S.; Cakir, M.; Arikan, C.; Tumgor, G.; Yuksekkaya, H.A.; Yilmaz, F.; Kilic, M. Liver transplantation for progressive familial intrahepatic cholestasis: Clinical and histopathological findings, outcome and impact on growth. Pediatr. Transplant. 2007, 11, 634–640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pose, E.; Piano, S.; Juanola, A.; Ginès, P. Hepatorenal Syndrome in Cirrhosis. Gastroenterology 2024, 166, 588–604.e1. [Google Scholar] [CrossRef] [Scilit]
- Bera, C.; Wong, F. Management of hepatorenal syndrome in liver cirrhosis: A recent update. Therap. Adv. Gastroenterol. 2022, 15, 17562848221102679. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maggiore, G.; de Giacomo, C. Efficacy of ursodeoxycholic acid in preventing cholestatic episodes in a patient with benign recurrent intrahepatic cholestasis. Hepatology 1992, 16, 504. [Google Scholar] [CrossRef] [Scilit]
- Helgadottir, H.; Folvik, G.; Vesterhus, M. Improvement of cholestatic episodes in patients with benign recurrent intrahepatic cholestasis (BRIC) treated with rifampicin. A long-term follow-up. Scand. J. Gastroenterol. 2023, 58, 512–520. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koukoulioti, E.; Ziagaki, A.; Weber, S.N.; Lammert, F.; Berg, T. Long-Term Colestyramine Treatment Prevents Cholestatic Attacks in Refractory Benign Recurrent Intrahepatic Cholestasis Type 1 Disease. Hepatology 2021, 74, 522–524. [Google Scholar] [CrossRef] [Scilit]
- Stapelbroek, J.M.; van Erpecum, K.J.; Klomp, L.W.; Venneman, N.G.; Schwartz, T.P.; van Berge Henegouwen, G.P.; Devlin, J.; van Nieuwkerk, C.M.; Knisely, A.S.; Houwen, R.H. Nasobiliary drainage induces long-lasting remission in benign recurrent intrahepatic cholestasis. Hepatology 2006, 43, 51–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huster, D.; Schubert, C.; Achenbach, H.; Caca, K.; Mössner, J.; Berr, F. Successful clinical application of extracorporal albumin dialysis in a patient with benign recurrent intrahepatic cholestasis (BRIC). Z Gastroenterol. 2001, 39, 13–14. [Google Scholar] [CrossRef] [Scilit]
- Bénichou, C. Criteria of drug-induced liver disorders. Report of an international consensus meeting. J. Hepatol. 1990, 11, 272–276. [Google Scholar] [CrossRef] [Scilit]
- Hayashi, P.H.; Lucena, M.I.; Fontana, R.J.; Bjornsson, E.S.; Aithal, G.P.; Barnhart, H.; Gonzalez-Jimenez, A.; Yang, Q.; Gu, J.; Andrade, R.J.; et al. A revised electronic version of RUCAM for the diagnosis of DILI. Hepatology 2022, 76, 18–31. [Google Scholar] [CrossRef] [Scilit]
- Soret, P.A.; Chazouillères, O.; Corpechot, C. Current approach to diagnosis and management of low-phospholipid associated cholelithiasis syndrome. Curr. Opin. Gastroenterol. 2025, 41, 67–73. [Google Scholar] [CrossRef] [Scilit]
- Flinders, B.; Huizing, L.R.S.; van Heerden, M.; Cuyckens, F.; Neumann, U.P.; van der Laan, L.J.W.; Olde Damink, S.W.M.; Heeren, R.M.A.; Schaap, F.G.; Vreeken, R.J. Cross-Species Molecular Imaging of Bile Salts and Lipids in Liver: Identification of Molecular Structural Markers in Health and Disease. Anal. Chem. 2018, 90, 11835–11846. [Google Scholar] [CrossRef] [Scilit]
- Moore, J.L.; Patterson, N.H.; Norris, J.L.; Caprioli, R.M. Prospective on Imaging Mass Spectrometry in Clinical Diagnostics. Mol. Cell. Proteom. 2023, 22, 100576. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Q.; Wu, Z.H.; Zhao, S.S.; Yang, J.; Chen, L.; Wang, X.Y.; Wang, Z.Y.; Liu, H.X. Identification and Spatial Visualization of Dysregulated Bile Acid Metabolism in High-Fat Diet-Fed Mice by Mass Spectral Imaging. Front. Nutr. 2022, 9, 858603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.; Bowman, A.P.; Buck, W.R.; Kohnken, R.; Good, C.J.; Wagner, D.S. Mass Spectrometry Imaging Distinguishes Biliary Toxicants on the Basis of Cellular Distribution. Toxicol. Pathol. 2025, 53, 55–64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chung, H.H.; Huang, P.; Chen, C.L.; Lee, C.; Hsu, C.C. Next-generation pathology practices with mass spectrometry imaging. Mass. Spectrom. Rev. 2023, 42, 2446–2465. [Google Scholar] [CrossRef] [Scilit] [PubMed]
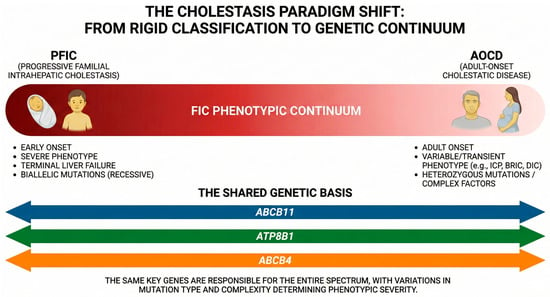
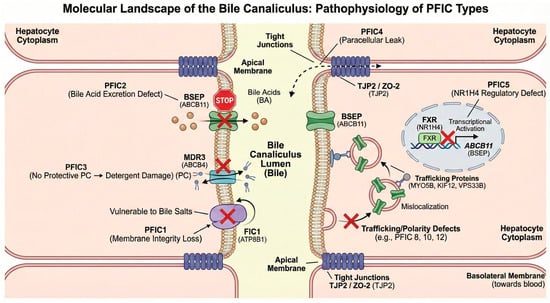
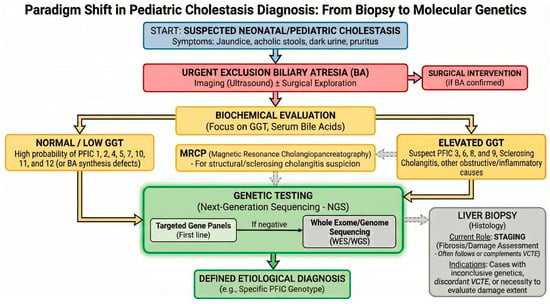
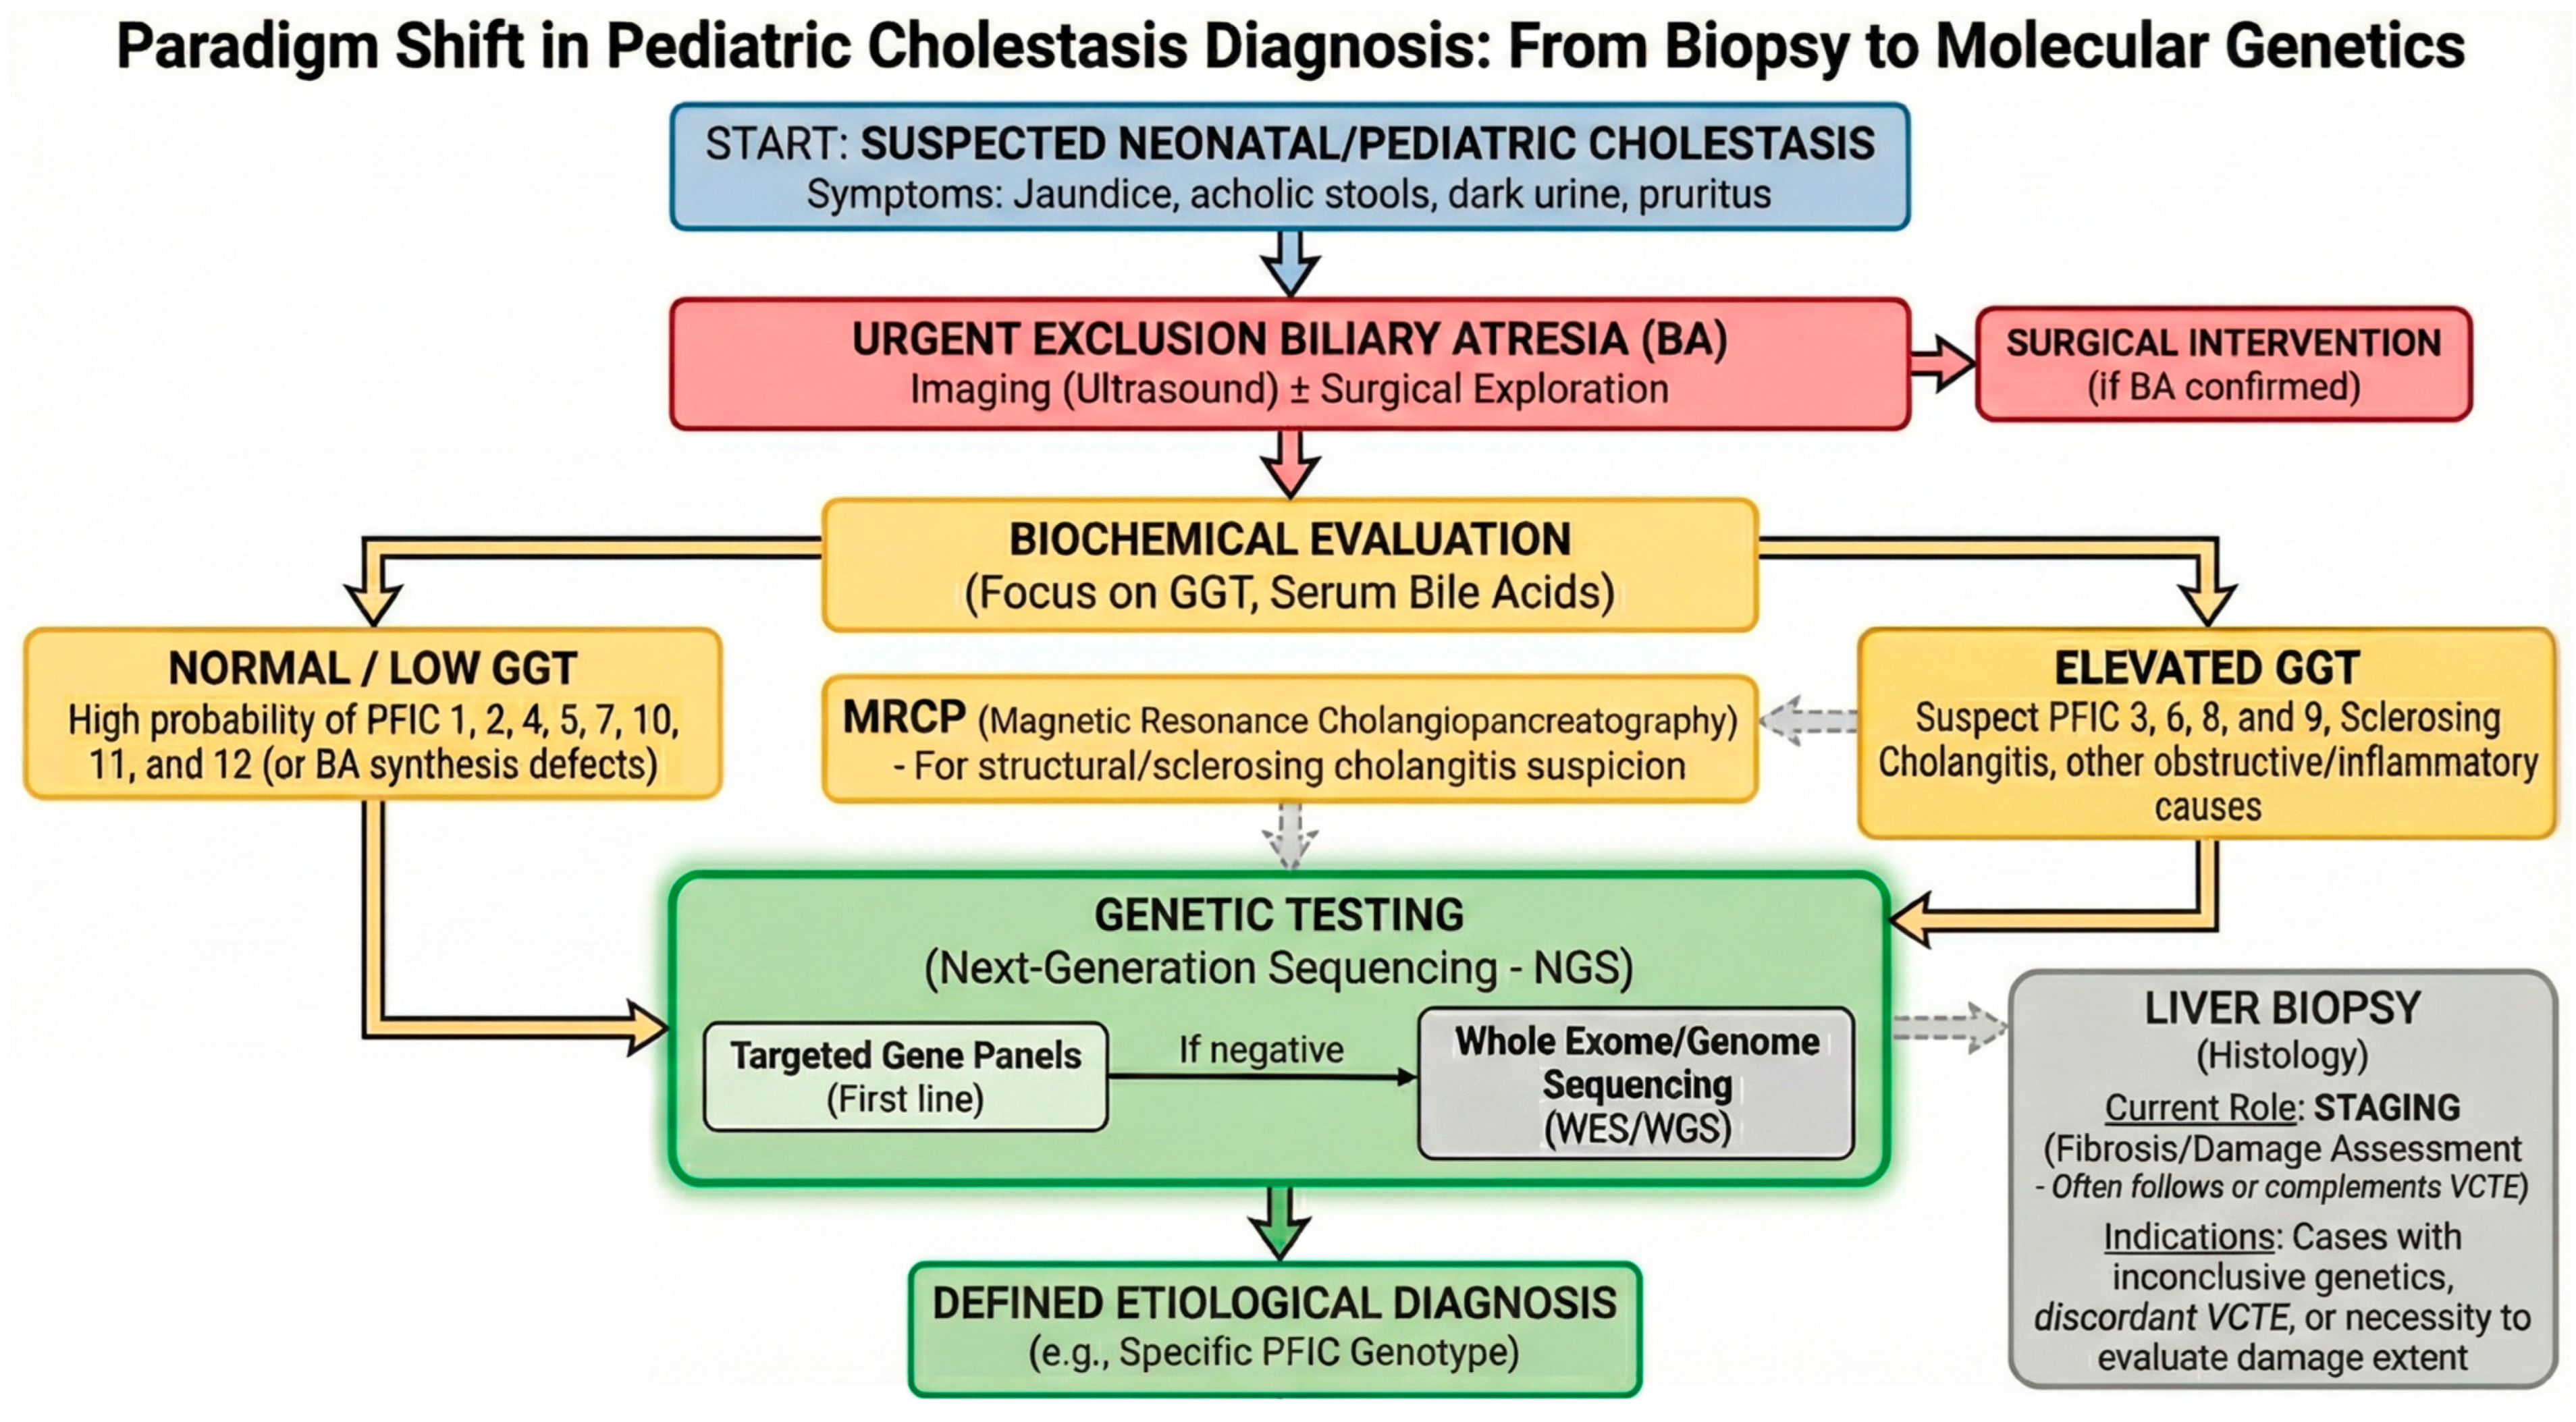
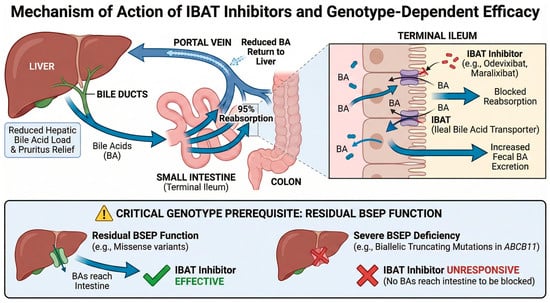
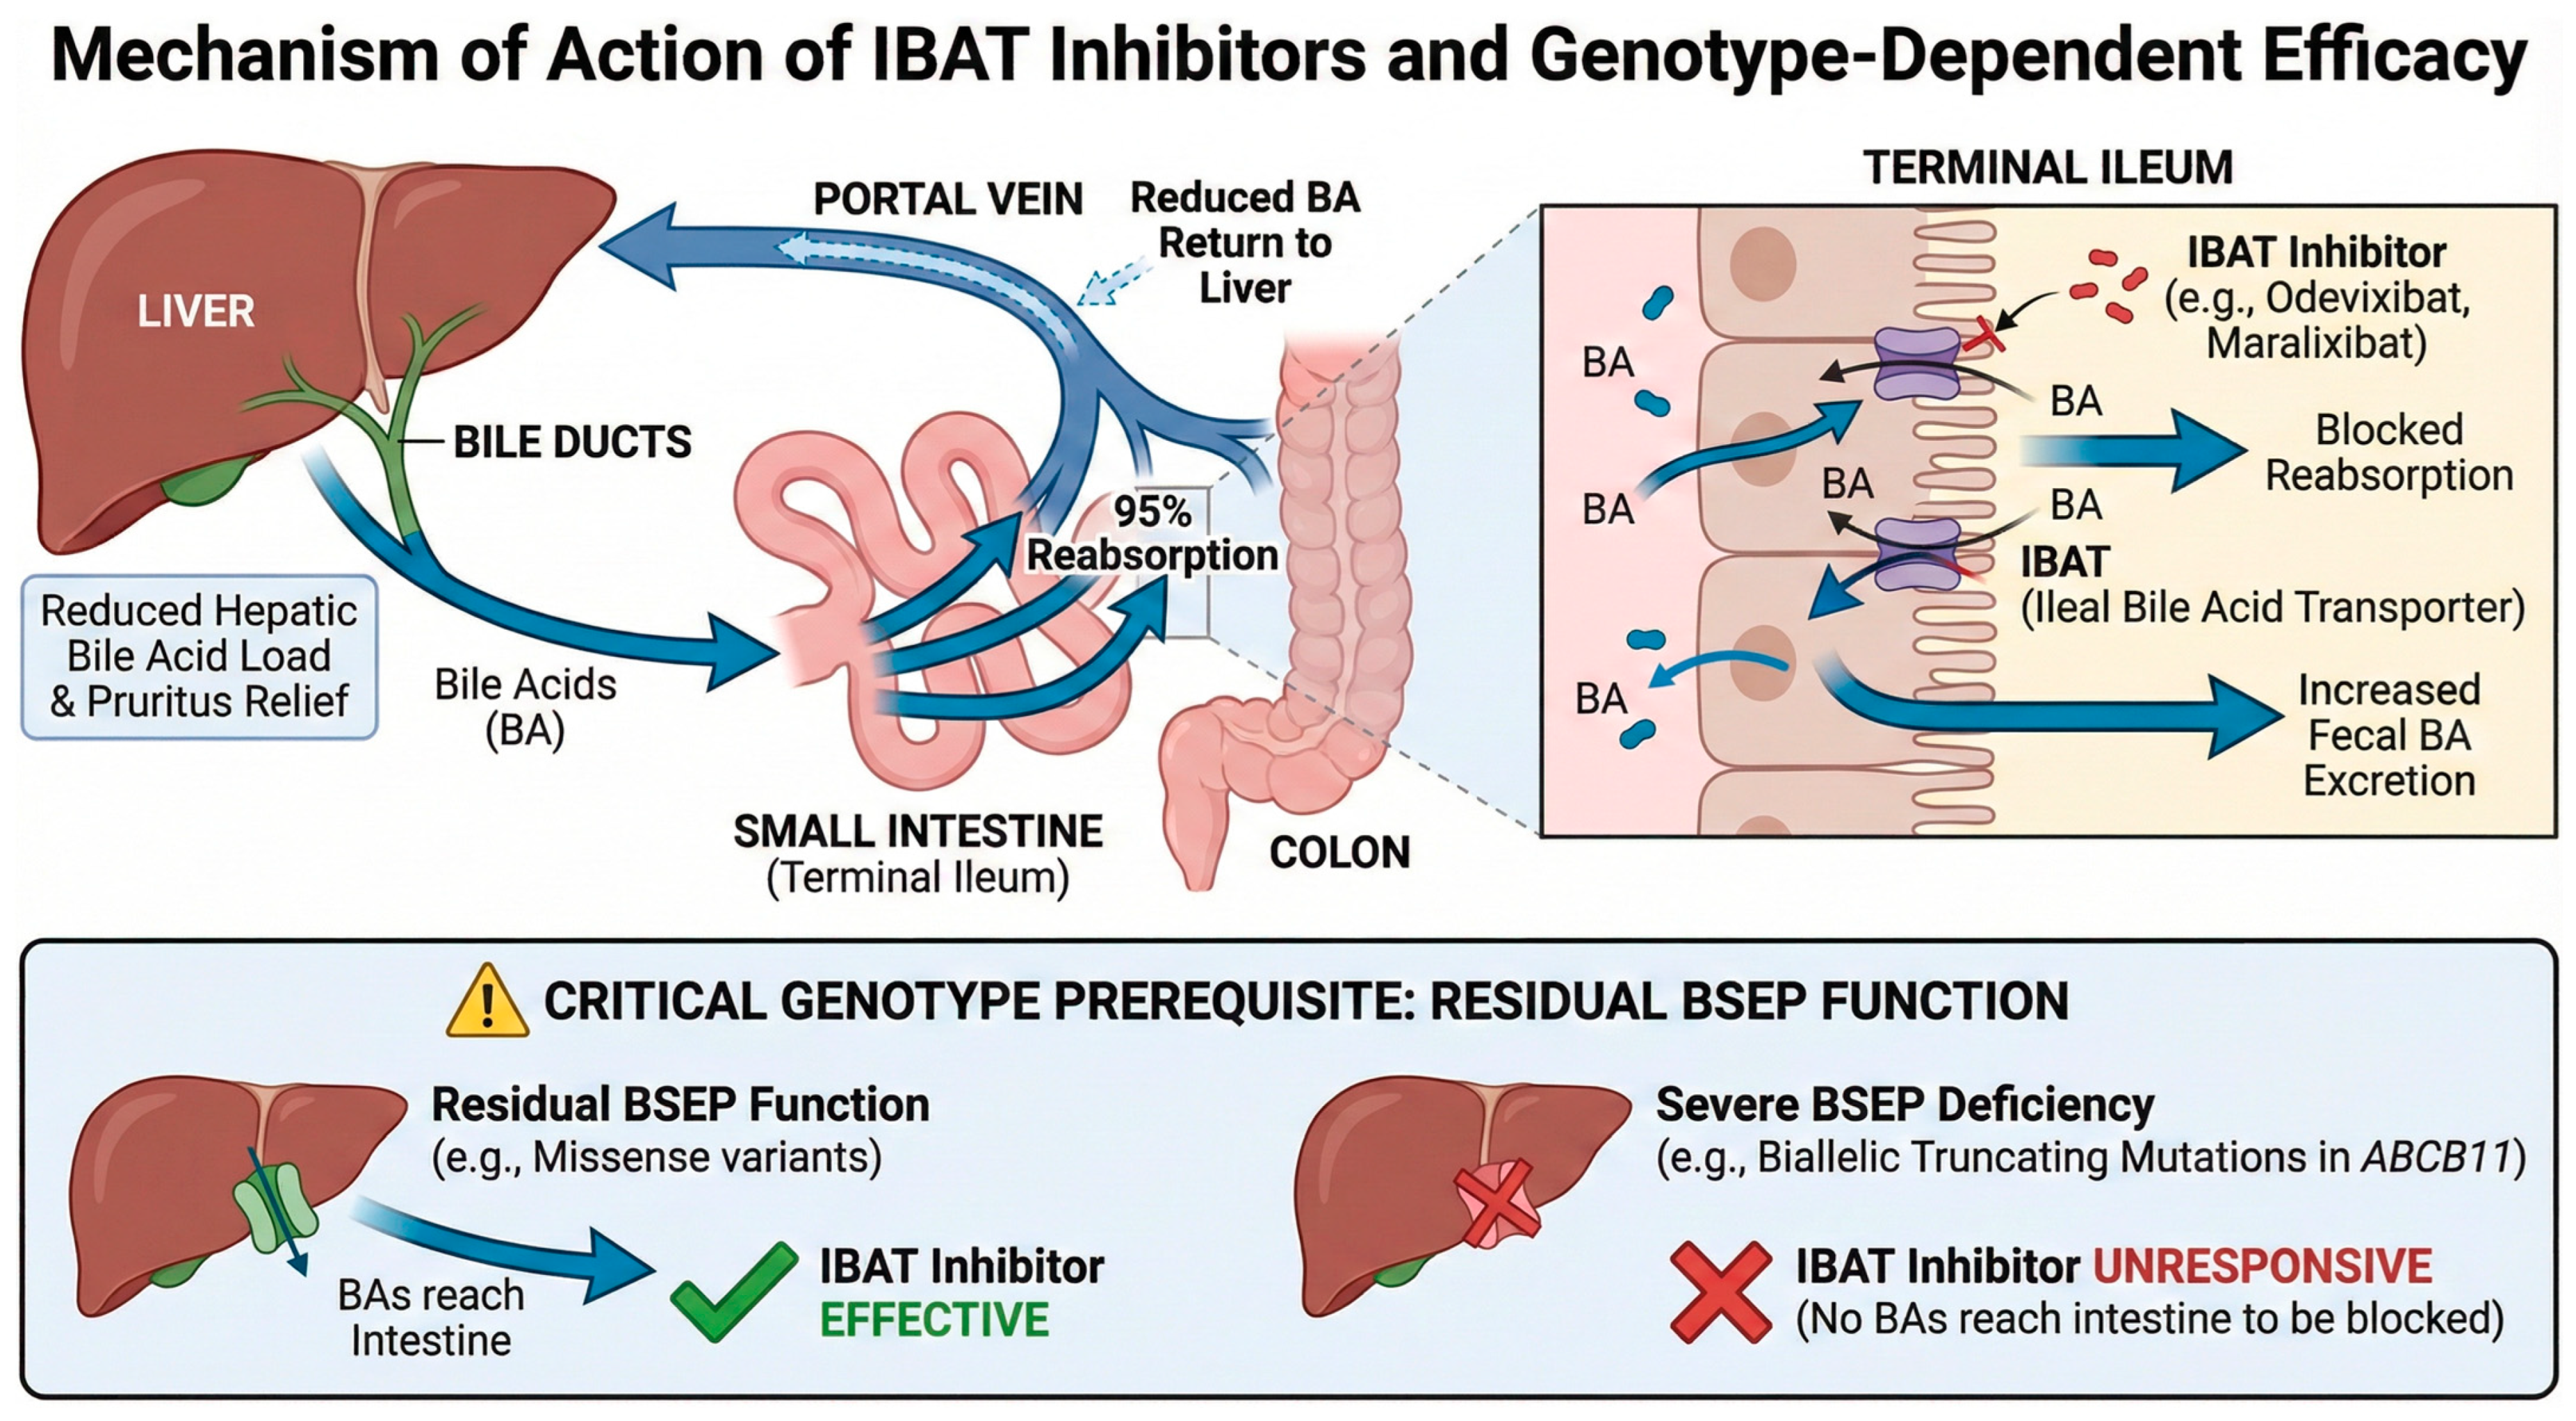

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.