Applying Artificial Intelligence to Childhood Obesity: T2DM and MASLD Risk Predictive Models


Abstract
1. Introduction
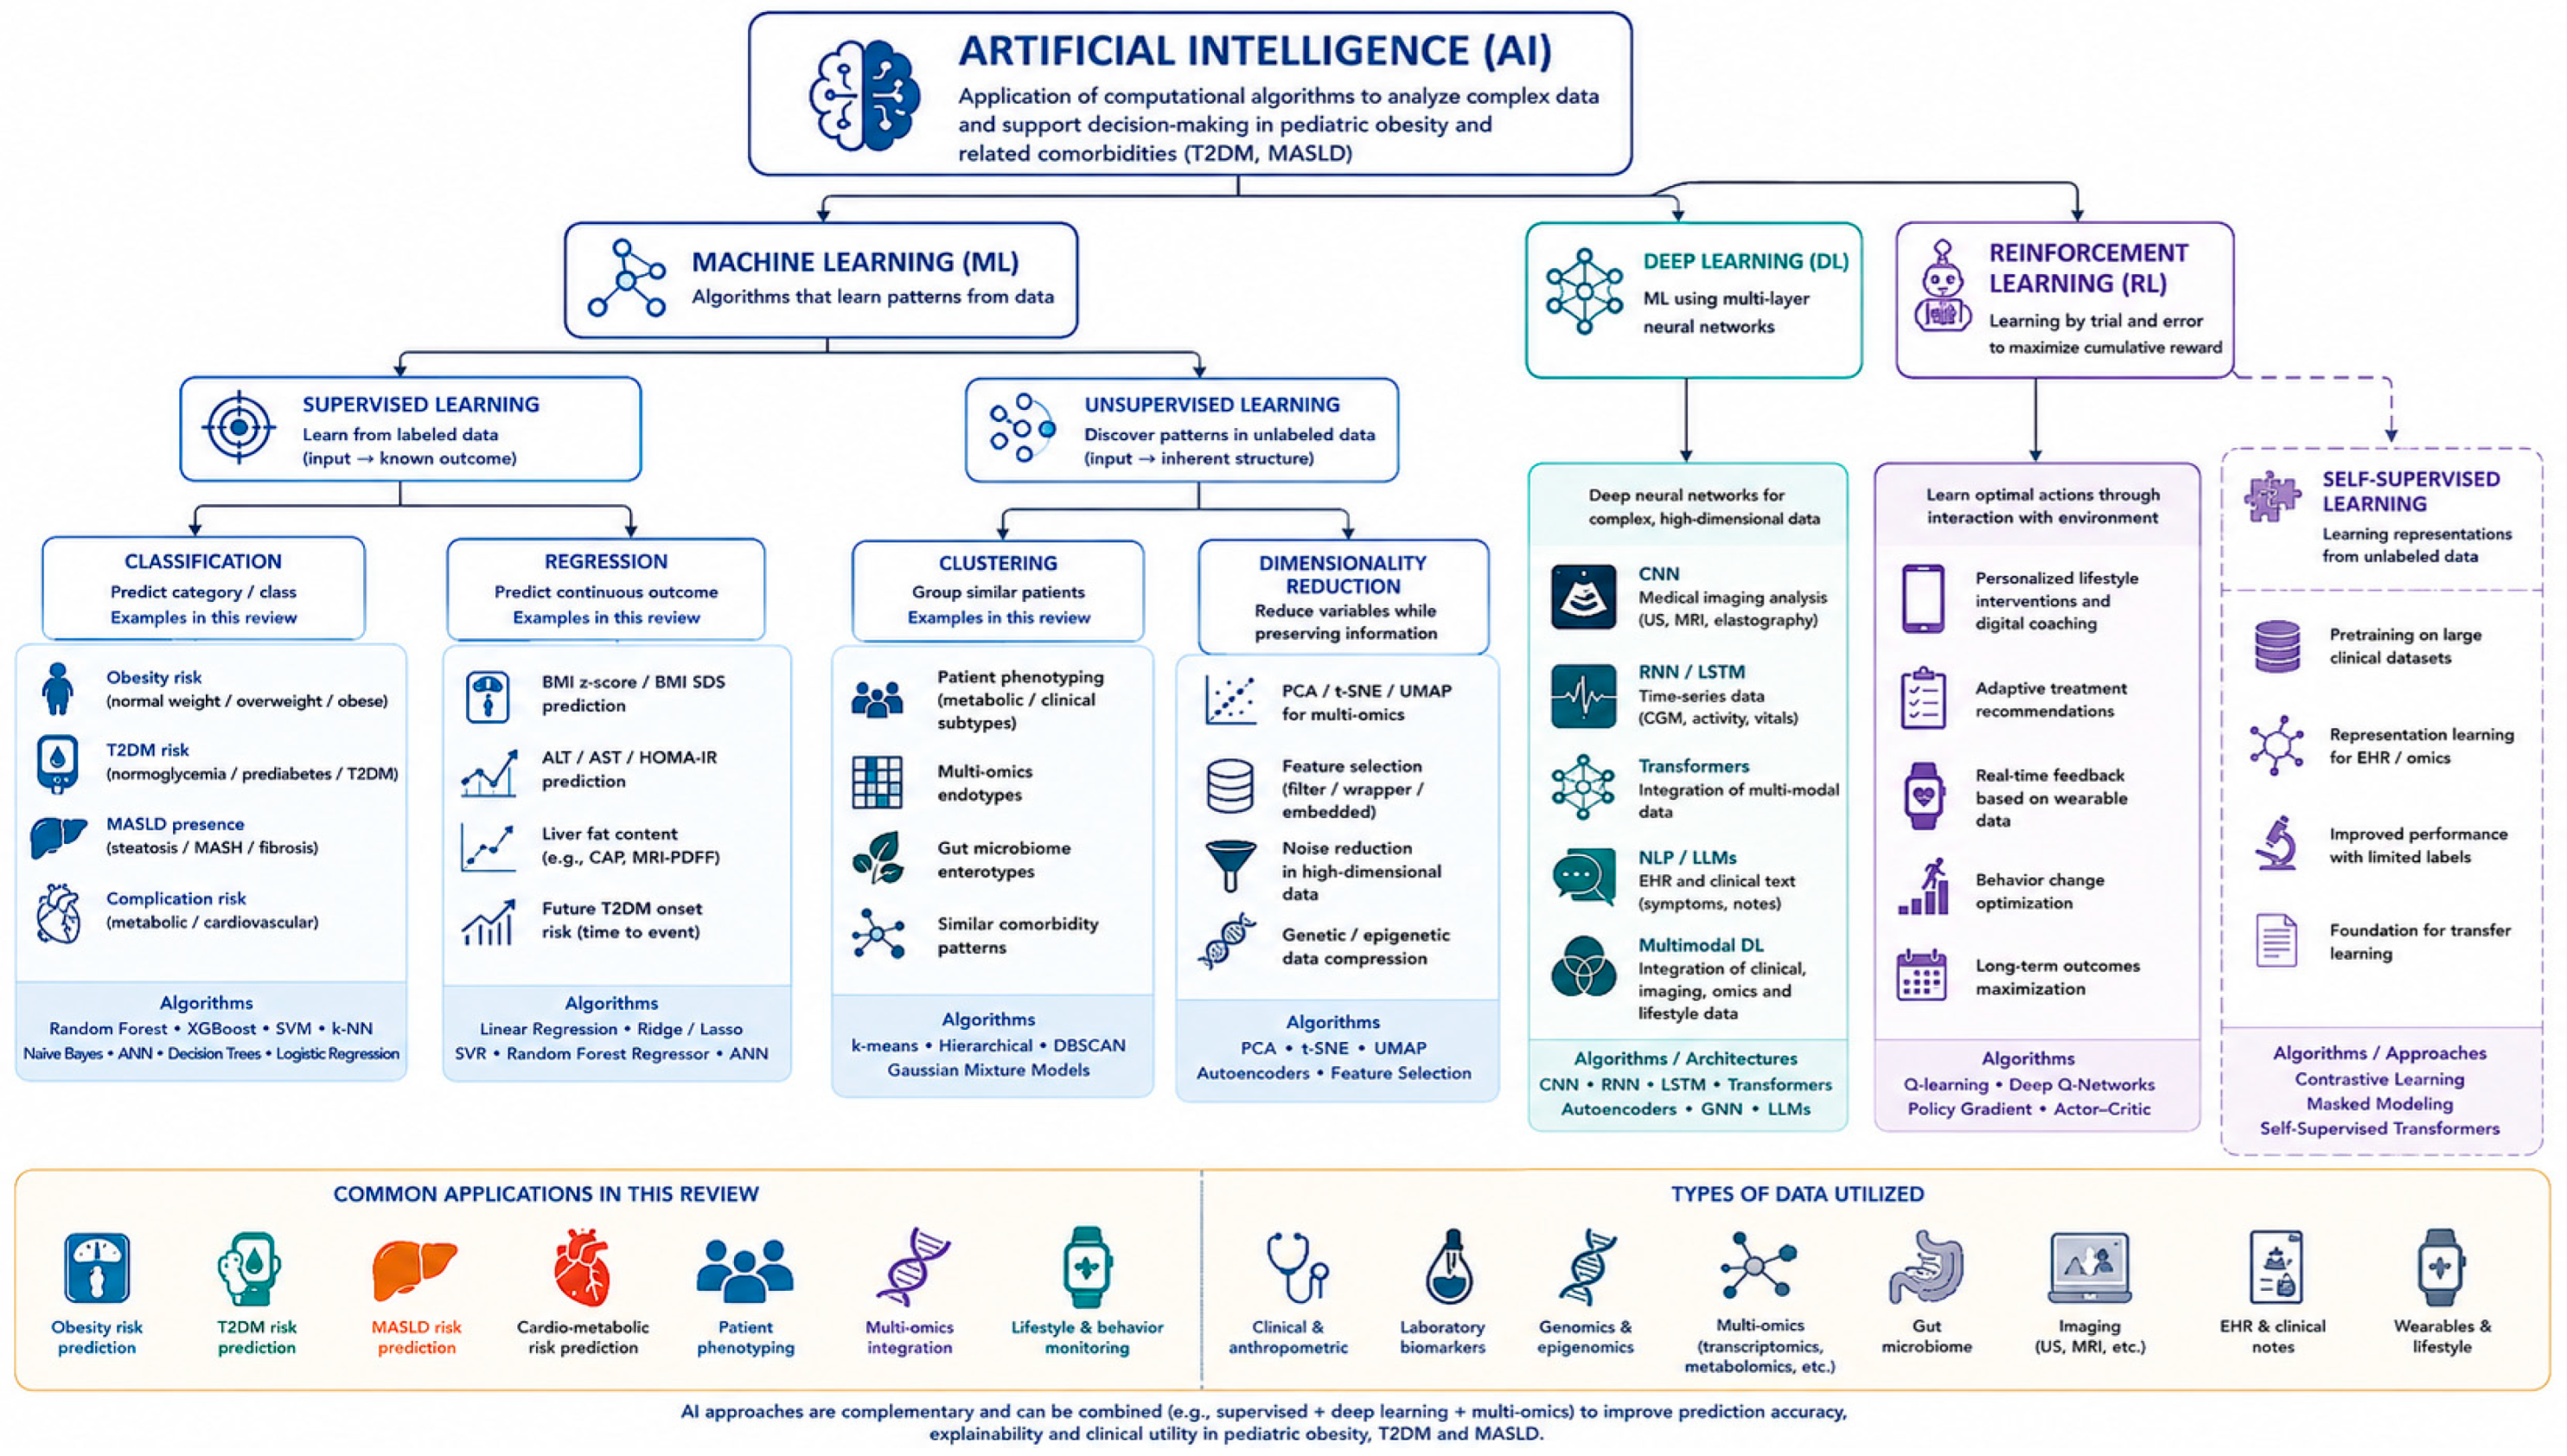
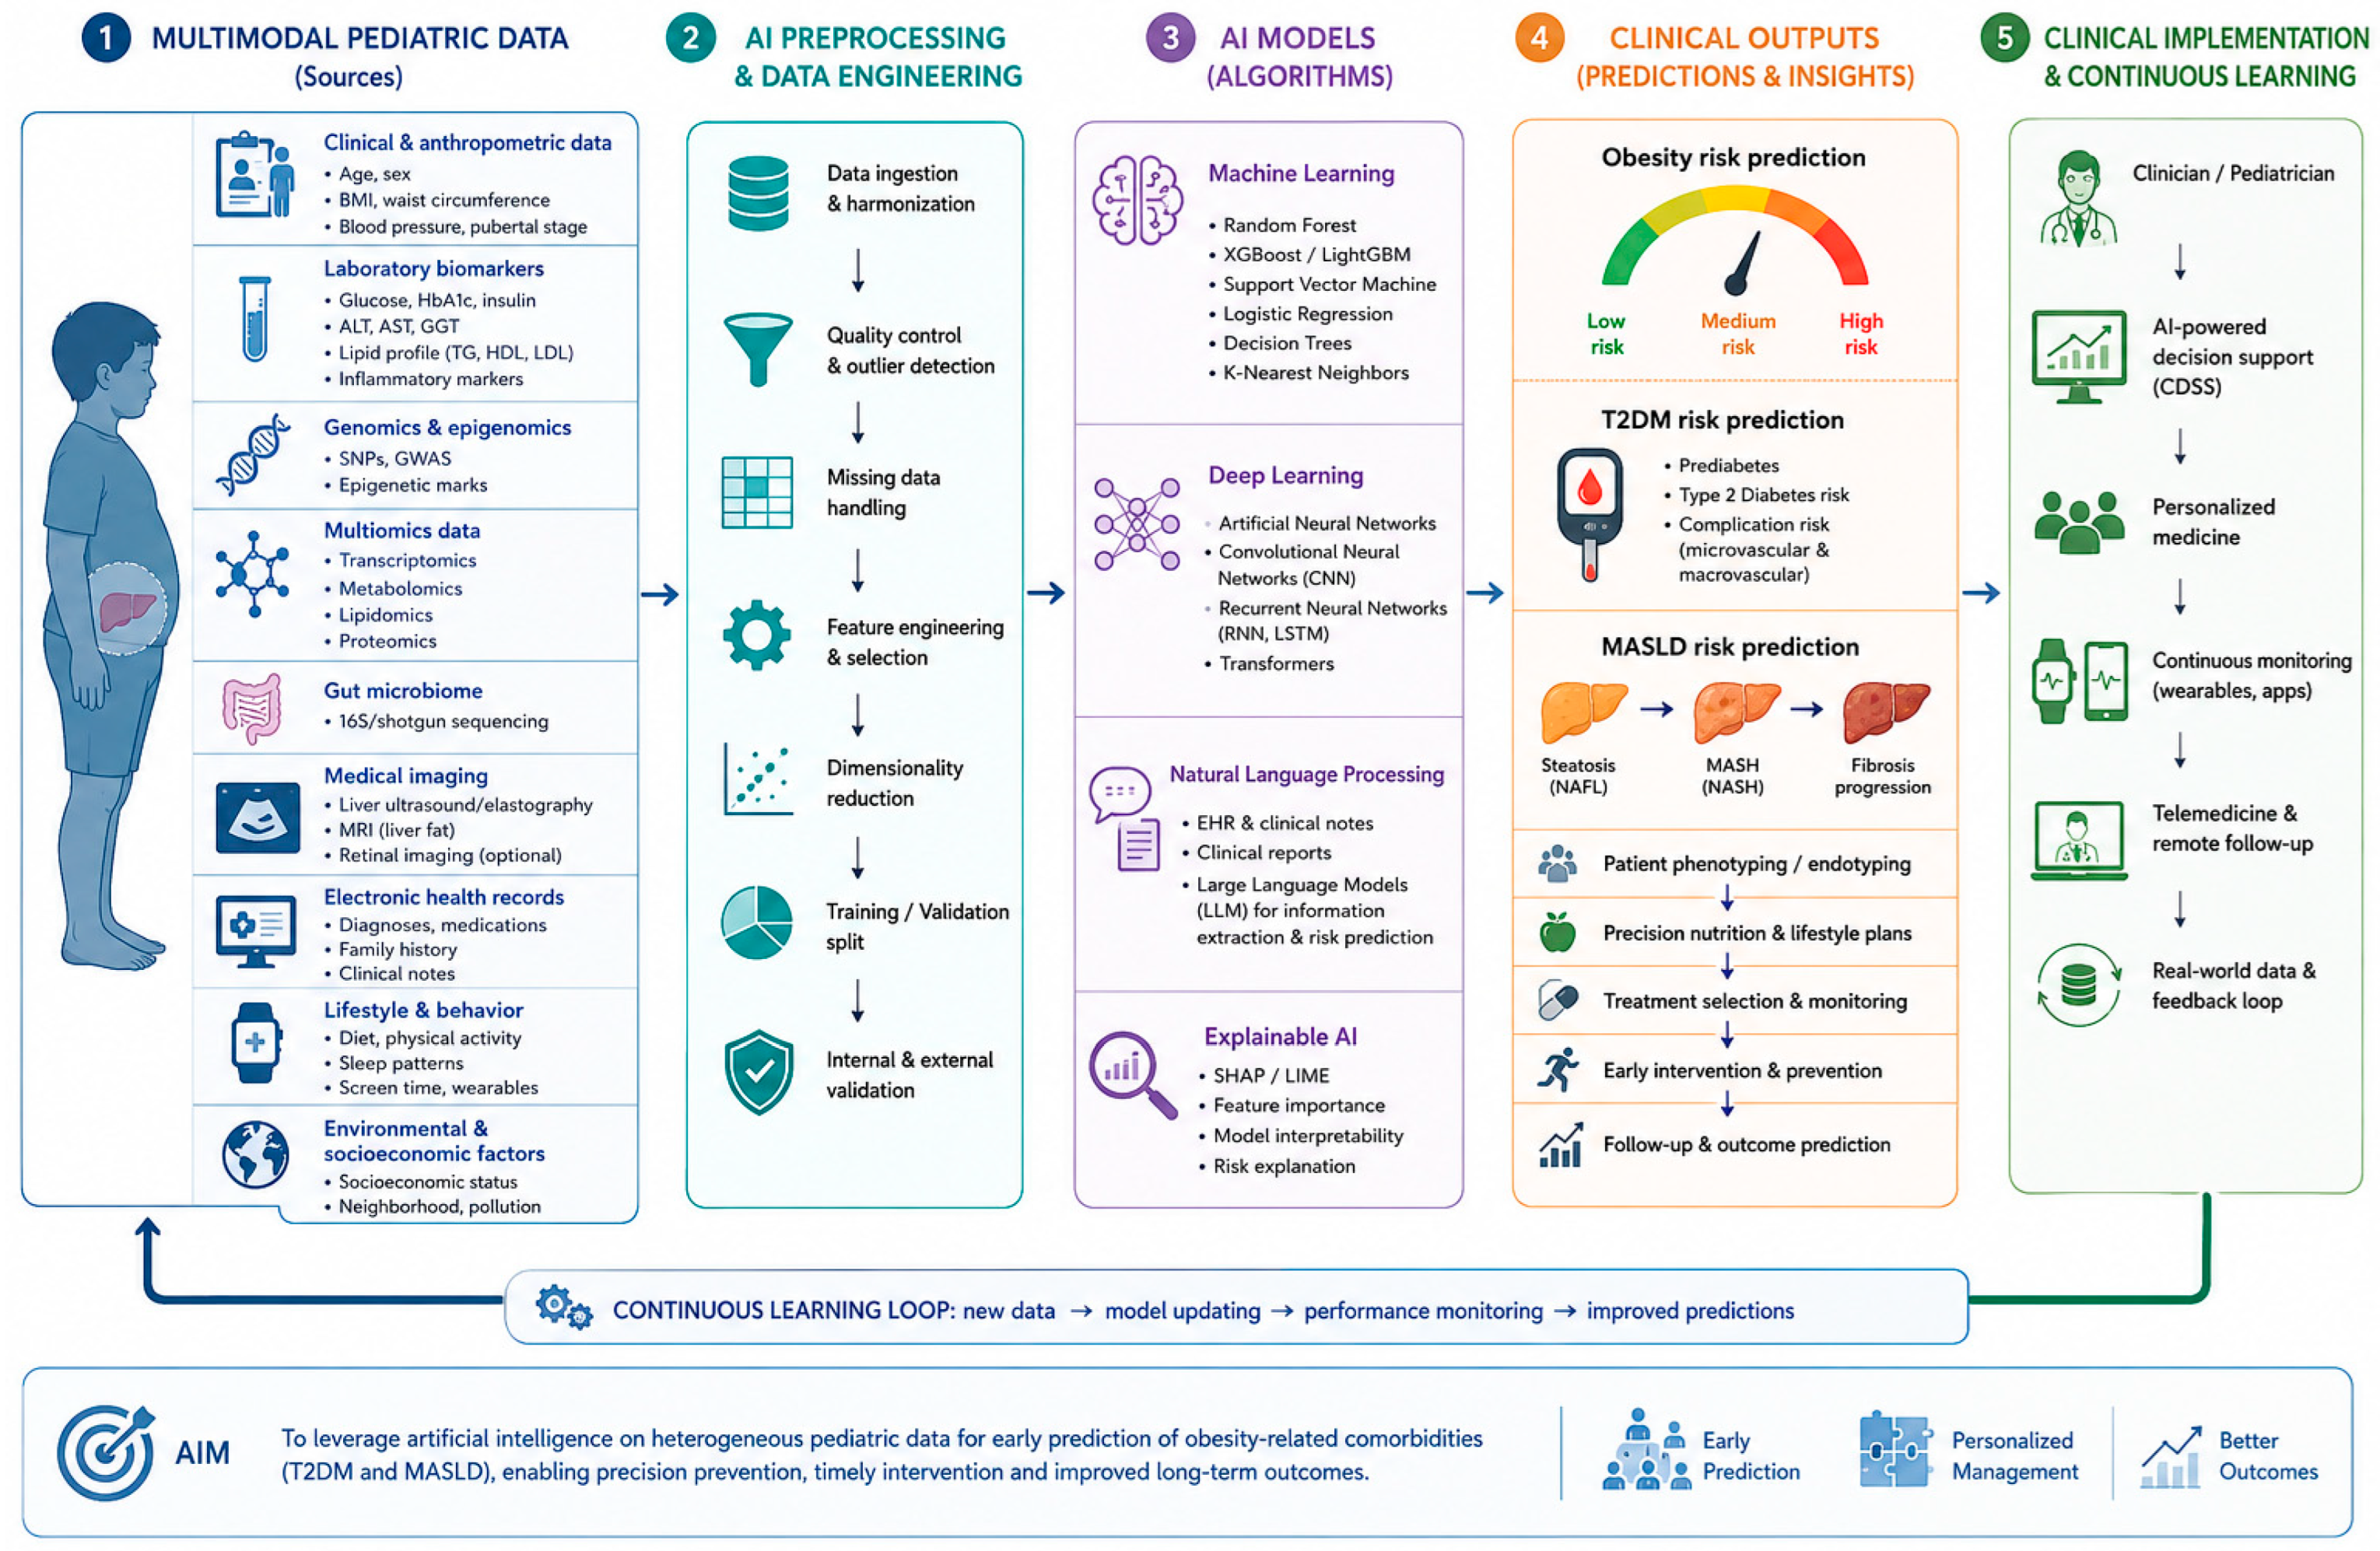
Artificial Intelligence Applied to Healthcare: Available Data Sources
2. Methods
3. Results
3.1. Predictive Models for the Diagnosis and Management of T2DM

| Article | Study Design: Prospective or Retrospective | Population: Exact Age Range and Characteristics | Model-Development Sample; Validation Sample; Internal and External Validation | Outcome Definition and Reference Standard | Predictor Variables | Algorithm | Discrimination Metrics | Calibration | Interpretability/Explainability | Clinical Availability/Deployment Status | Pediatric Applicability |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Yang et al., 2025 [41] | Design: Single-center observational study; participants recruited July 2023–February 2024 with at least 1 year of follow-up, data abstracted from clinical records. NOTE: The Limitations section of the paper describes the study as retrospective, which is inconsistent with the enrolment-plus-follow-up description in the Methods section. Timing: Retrospective per the authors’ own Limitations statement; data abstracted from case records. | Children with obesity aged <18 years attending endocrinology outpatient clinics/wards, Children’s Hospital of Soochow University, Suzhou, China. n = 292 analyzed (300 enrolled, 8 excluded for missing data). Mean age 11.96 (SD 2.29) y; 162/292 (55.5%) male. Obesity defined by weight-for-height >20% above the reference (Zhufutang Practical Pediatrics, 8th ed), NOT by BMI z-score/percentile. No T2DM 11.79 (2.26) y vs. T2DM 12.80 (2.25) y, p = 0.005. | Development: n = 292; random split 75% training/25% internal validation; 10-fold cross-validation within the training set. 49 outcome events (16.8%) → approx. 4–5 events per candidate predictor (8 predictors). No sample size calculation reported. Validation: Internal only (random 25% hold-out set + 10-fold CV). NO external validation. Authors state multi-center external validation is planned. Internal/external: Internal: 75/25 random split plus 10-fold CV. External: None. | T2DM diagnosed by ADA/ISPAD criteria (symptoms plus FPG ≥ 7.0 mmol/L, or 2 h post-load glucose ≥ 11.1 mmol/L, or HbA1c ≥ 6.5%, or random glucose ≥ 11.1 mmol/L; abnormal values confirmed on retesting when asymptomatic). Diabetes type assigned in a second step using GAD, IA-2, ZnT8 and insulin autoantibodies, with genetic testing for MODY where indicated. Reference standard: Clinical/biochemical ADA-ISPAD criteria. | 8 predictors selected by univariable comparison then logistic regression: BMI, creatinine, prealbumin, 180 min OGTT glucose, HbA1c, thyrotropin, total T4, free T4. | 8 algorithms compared: DT, LR, SVM, MLP, AdaBoost, RF, GBDT, XGBoost. SVM selected as final model (RBF kernel, C = 10). SMOTE oversampling applied to the training set; median/mode imputation; standardization; one-hot encoding; grid search. | SVM AUC 0.904 with accuracy 0.9322, recall 0.600, F1 0.750, CV accuracy 0.983 . Highest AUC of any model was MLP 0.961. | Not assessed. No calibration plot, calibration slope/intercept, Brier score or Hosmer–Lemeshow test reported. A nomogram was constructed from the model results but its calibration is not reported. | None applied. No SHAP, LIME or equivalent, despite the Introduction describing the model as “interpretable”. Interpretation is limited to logistic regression coefficients and a nomogram. | None. Research prototype; no software, no regulatory approval, no prospective clinical use. | Fully pediatric (<18 y) and obesity-specific—the only such T2DM model in this review. Transportability limited by the single Chinese center, small sample, non-standard obesity definition and reliance on a 180 min OGTT sample that is not part of routine pediatric practice. |
| Zou et al., 2018 [40] | Design: Retrospective cross-sectional diagnostic classification study using routine hospital physical-examination records (Luzhou, China), plus a secondary analysis of the public Pima Indians Diabetes dataset. Timing: Retrospective; secondary use of routine examination records and a public dataset. | Luzhou dataset: Attendees of routine hospital physical examinations, China. After deletion of abnormal and missing records, there were 151,598 diabetes and 69,082 healthy records. Age, sex and BMI distribution not reported. Pima dataset: Females of Pima Indian heritage aged ≥ 21 y; 768 records reduced to 392 after deletion of missing data. Neither dataset is obesity-defined. | Development: Five balanced training sets, each 68,994 healthy plus 68,994 diabetes records (i.e., approx. 137,988 records per draw); results averaged over the 5 draws. NOTE: The current Table 1 entry “68,994 subjects” refers to one class only. Validation: Five-fold cross-validation (internal). Separate hold-out “independent test set” of 13,700 records drawn from a second physical-examination dataset at the same source. Pima dataset analyzed separately with 10-fold CV; it was not used to validate the Luzhou model. Internal/external: Internal: 5-fold CV plus a same-source hold-out test set. External: none (no independent population/setting). | Prevalent “diabetes mellitus” as labeled in the source database. The basis on which labels were assigned is NOT described. Diabetes type was not distinguished—the authors state explicitly that they cannot predict the type of diabetes. No T2DM-specific reference standard. | Luzhou: 14 routine indices-age, pulse rate, respiratory rate, left/right systolic and diastolic pressure, height, weight, physique index (BMI), fasting glucose, waistline, LDL, HDL. Pima: 8 standard attributes. Dimensionality reduction by PCA and mRMR. | J48 DT (WEKA), RFt, and a two-layer feed-forward neural network with 10 hidden neurons (MATLAB). | No AUC or C-statistic reported . Luzhou 5-fold CV, all features: RF accuracy 0.8084, sensitivity 0.8495, specificity 0.7673, MCC 0.6189 (best of the three classifiers). Same-source hold-out test, all features: RF accuracy 0.8963, sensitivity 0.9226, specificity 0.8700, MCC 0.7937. Pima 10-fold CV best accuracy 0.7852 (mRMR + RF). | Not assessed. | Partial: DT structures displayed, information-gain based splits, and mRMR feature ranking. No SHAP/LIME or other post hoc explanation method. | None. The Pima dataset was made available online; no model, software or tool was deployed. | None. Age not reported for the Luzhou dataset; the Pima dataset is restricted to women aged ≥ 21 y. No pediatric data and no obesity-specific analysis. |
| Sun et al., 2025 [42] | Design: Cross-sectional community-based study, Heze City, Shandong, China; recruitment 2018–2019 by multistage stratified random sampling. Timing: Cross-sectional; data collected 2018–2019, analyzed retrospectively. No temporal separation between predictors and outcome. | 982 men aged ≥ 60 y (mean approx. 74.4, SD 8.6 y). Male sex only. 453 (46.1%) rural, 529 (53.9%) urban. Mean BMI 26.7–26.9 kg/m2; general obesity present in 52% and central obesity in 46–51%, but the cohort is NOT obesity-selected. Exclusions: Type 1 diabetes, severe cardiovascular/renal/hepatic disease, cognitive impairment, metabolically active medication. | Development: 982 participants; no separate development/validation split. XGBoost trained on the full dataset with 5-fold cross-validation and grid-search hyperparameter tuning. Validation: Internal only (5-fold CV plus sensitivity analyses stratified by BMI and energy-intake quartile). The authors state explicitly that no independent external validation dataset was available. Internal/external: Internal: 5-fold CV. External: None. | T2DM defined by ADA criteria: FPG ≥ 7.0 mmol/L, HbA1c ≥ 6.5%, self-reported physician diagnosis, or current antidiabetic medication. Prevalence reported as 48.37% “newly diagnosed”. CAUTION: The paper’s own Table 1 shows no difference in FPG (135.4 vs. 135.0 mg/dL, p = 0.39) or HbA1c (6.96 vs. 7.02%, p = 0.16) between the T2DM and non-T2DM groups, and approximately 50% of both groups were taking antidiabetic medication—internally inconsistent with the stated outcome definition and with the “newly diagnosed” label. | Data-driven dietary patterns (81-item validated semi-quantitative FFQ collapsed into 21 food groups, then UMAP + k-means clusters: high-fiber nutrient-dense, staple-protein, seafood-eggs, sugary and processed foods), total energy intake, physical activity (IPAQ, MET-h/week), demographics, anthropometry, blood pressure, and biochemistry. | UMAP (dimensionality reduction) + k-means (dietary pattern clustering); XGBoost classifier for T2DM; SHAP for model interpretation; multivariable logistic regression for associations. | XGBoost, 5-fold CV: Mean ROC AUC 0.83, accuracy 84%). No discrimination metric is currently reported for this study | Not assessed. | SHAP applied (summary, waterfall and force plots) identifying dietary patterns, total energy intake and physical activity as the leading contributors. | None. | None. Men aged ≥ 60 y only; the authors note that generalizability to women and other age groups is unknown. Least-applicable study in Table 1 to a pediatric obesity review. |
| Nomura et al., 2021 [43] | Design: Retrospective analysis of annual specific health checkup records, Kanazawa City, Japan, 2008–2018. Timing: Retrospective. | 509,153 annual health checkup records from 139,225 individuals; 65,505 individuals without diabetes at baseline formed the analysis set. Age range, sex distribution, BMI and obesity status not reported in the paper. | Development: 65,505 individuals split 6:2:2 into training (36,303), tuning (13,101) and testing (13,101). 4696 incident diabetes cases (7.2%). Validation: Internal only (hold-out test set, with 1000-iteration bootstrap for confidence intervals). No external validation. Internal/external: Internal: 6:2:2 split with bootstrap CIs. External: None. | New onset of diabetes mellitus during annual health checkups. The precise diagnostic criteria and whether T2DM was distinguished are not reported in the paper. | Physical examination measurements, blood and urine tests, and participant questionnaires from the annual checkups. The specific variables entered into the model are not reported in the paper. | Gradient-boosting DTs. | Test set: AUC 0.71 (95% CI 0.69–0.72); precision 75.3% (71.6–78.8); recall/sensitivity 42.2% (39.3–45.2); F1 54.1% (51.2–56.7); accuracy 94.9% (94.5–95.2). NOTE: Accuracy is inflated by the 7.2% event rate and should not be read as a measure of usefulness. | Not reported. | Not reported. | Not reported. | None—annual specific health checkups in Japan target adults (≥40 y for the standard program). No pediatric data. |
| Cardozo et al., 2022 [44] | Design: Retrospective cross-sectional diagnostic/screening study using a routine clinical laboratory database (Santa Luzia Medical Laboratory, Florianopolis, Brazil). Timing: Retrospective; secondary use of an existing laboratory database. | 62,496 patients undergoing routine laboratory testing. Age 19–99 y; mean 56.7 (SD 16.2) y; 43.4% male, 56.6% female. HbA1c categories: 47.60% healthy, 37.95% prediabetes, 14.45% diabetes. Not obesity-selected; BMI was not available (laboratory variables only). | Development: 80% of 62,496 (approx. 49,997) for training, of which 30% was reserved for hyperparameter tuning by Bayesian optimization with a Gaussian process. Validation: Internal only: 20% random hold-out test set (approx. 12,499). No external validation. Internal/external: Internal: 80:20 split with a nested tuning subset. External: None. | Glycated hemoglobin category as the reference standard: healthy <5.7%, prediabetes 5.7–6.4%, diabetes ≥ 6.5%. Single HbA1c measurement without confirmatory testing. Diabetes type NOT distinguished; the target is HbA1c-defined diabetes status, not T2DM specifically. | 15 routine laboratory variables selected by factor analysis: age, creatinine, fasting plasma glucose, basophils %, MCHC, MCH, haematocrit, leucocytes, lymphocytes %, monocytes %, MPV, platelets, RDW, segmented neutrophils %, MCV. Fasting plasma glucose is itself a diabetes diagnostic test. | Five classifiers (KNN, SVM, naïve Bayes, RF, ANN) and their regression counterparts predicting HbA1c as a continuous value followed by classification; three dataset arrangements (healthy/prediabetes/diabetes; healthy vs. not healthy; no diabetes vs. diabetes). | No AUC OR C-statistic reported. Best overall result, ANN on the healthy vs. not-healthy arrangement: sensitivity 78.1%, precision 78.7%, F1 78.4%. On the no-diabetes vs. diabetes arrangement: ANN sensitivity 67.9%, specificity 97.9%, precision 84.8%; RF sensitivity 66.3%, specificity 98.1%, precision 85.7%; KNN precision 93.7% with sensitivity 42.7%. Best regression MSE 0.29 (ANN). | Not assessed. | Minimal: factor analysis for feature selection and confusion matrices. No SHAP, LIME or equivalent. | Not deployed. Proposed as a laboratory-side screening alert to trigger confirmatory HbA1c testing; the authors state explicitly that the approach is not recommended for diagnostic purposes. | None. Adults aged 19/20–99 y; no pediatric data and no obesity-related variables. |
| Li et al., 2025 [47] | Design: Systematic review and meta-analysis of ML-based prediction models (PRISMA-DTA, CHARMS and TRIPOD applied; protocol registered INPLASY202490038). Databases searched to 18 April 2024. NOT A PRIMARY PREDICTION MODEL STUDY. Timing: The included studies were predominantly retrospective. | 26 included studies, 94 ML models. Adults with T2DM; 14 cohort, 9 cross-sectional, 3 case–control designs, predominantly retrospective and single-center. Countries: China 14, USA 4, Singapore 3, Iran 3, Italy 1, Bangladesh 1. Individual study sample sizes range from 133 to 147,664; reported mean ages of included cohorts are approximately 51–64 y. No pediatric study was included. | Development: Not applicable at the review level. Across the included studies, 81 models were assessed in internal validation sets (total internal validation sample 319,190 participants) and 13 in external validation sets. Validation: 25/26 studies performed internal validation (hold-out or k-fold); only 8/26 performed external validation—4 with genuinely independent datasets, 3 with temporal splits and 1 partially independent. Combined external validation sample 37,944 across 7 studies. Internal/external: See validation columns: internal 25/26 studies; external 8/26 studies. | Diabetic kidney disease in patients with T2DM (albuminuria and/or reduced eGFR). 18 of the included models were diagnostic and 8 prognostic; prognostic follow-up ranged from 1 year to a median of 7.8 years. | Across studies: demographics, medical history, diabetes duration, complications, lifestyle, physical examination, laboratory tests, and in some studies circulating metabolites, genetic parameters, retinal photographs, renal ultrasound and renal pathology images. Predictor selection most often by RFECV or LASSO. | Pooled across traditional regression ML, general ML and deep learning. Individual algorithms included LR, RF, DT, SVM, GBDT, XGBoost, LASSO, Bayesian networks, naïve Bayes, AdaBoost, KNN and deep learning models. | Pooled AUC 0.839 (95% CI 0.787–0.890) in internal validation sets, with I2 = 99.8% and a 95% prediction interval of 0.56 to 1.00; pooled AUC 0.830 (95% CI 0.784–0.877) in external validation sets. Subgroups: Traditional regression ML 0.797 (0.777–0.816), general ML 0.811 (0.785–0.836), deep learning 0.863 (0.825–0.900). RF was the best-performing individual algorithm, pooled AUC 0.848 (95% CI 0.785–0.911). The very wide prediction interval means performance in a new setting could be no better than chance. | Not pooled. The review reports that 14 of the 26 included studies failed to assess discrimination and calibration adequately. | Not extracted or synthesized by the review. | None of the included models had reached clinical deployment. | None. All included studies were conducted in adults with T2DM; no pediatric evidence. |
| Anjana et al., 2020 [49] | Design: Retrospective analysis of an electronic medical record database from a network of 50 diabetes centers across 9 Indian states, with longitudinal follow-up for complications; replication of the clustering in the nationally representative ICMR-INDIAB population survey. Unsupervised phenotyping study, NOT a prediction model study. Timing: Retrospective derivation from EMR data with prospective longitudinal follow-up for complication outcomes. | 19,084 individuals with T2DM aged 10–97 y with diabetes duration <5 y at first clinic visit (mean duration 1.74, SD 1.4 y). Selection: 373,000 records with T2DM → 55,429 with complete baseline variables → 20,850 with duration <5 y → exclusion of implausible HOMA values (n = 1512), 5SD outliers (n = 188) and GAD-antibody-positive individuals (n = 66) → 19,084. Mean age at diagnosis by cluster 42.1–50.2 y; 58.6–73.7% male; mean BMI by cluster 24.9–32.6 kg/m2. | Development: 19,084 for the k-means clustering (derivation). Validation: Replication in ICMR-INDIAB, a nationally representative population-based survey across 15 Indian states: 3851 individuals with T2DM, 2204 after exclusions, clustered on 6 of the 8 variables (C-peptide unavailable). Internal/external: Internal: Bootstrap stability (Jaccard index > 0.75), silhouette width, sex-stratified re-clustering, sensitivity analyses at diabetes duration <1, <3 and <5 y. External: Replication in ICMR-INDIAB (n = 2204). | Not a predicted outcome but incident microvascular complications analyzed by Cox regression: retinopathy (four-field stereo color fundus photography graded by a retinal specialist using a modified ETDRS system), nephropathy (micro- or macroalbuminuria), CKD (eGFR <60 mL/min/1.73 m2, CKD-EPI) and diabetic kidney disease (CKD and/or albuminuria). T2DM itself defined by absence of ketosis, fasting C-peptide > 0.6 pmol/mL, absence of pancreatic calculi and response to oral agents for at least 2 y. | Eight clustering variables: age at diagnosis, BMI, waist circumference, HbA1c, serum triglycerides, HDL cholesterol, and fasting and stimulated C-peptide. | k-means clustering (k = 4, max 10,000 iterations, R 3.6.0) on scaled and centered values; Hopkins statistic for clustering tendency; silhouette width for the number of clusters; Jaccard bootstrap (2000 resamples) for cluster stability; Cox proportional hazards models for complications adjusted for age at diagnosis and sex. | Not applicable-no individual-level risk prediction model, therefore no AUC or c-statistic. Four clusters identified: SIDD 26.2%, IROD 25.9% (novel), CIRDD 12.1% (novel), MARD 35.8%. SIDD had the highest hazard for retinopathy, followed by CIRDD; CIRDD had the highest hazard for kidney disease. | Not applicable (no predicted probabilities). | Inherently interpretable: clusters are defined by eight routine clinical and biochemical variables, with published cluster means and formal stability statistics. | None. Phenotypic classification proposed for research and risk stratification, not implemented as a tool. | Minimal. The eligible age range began at 10 y, so adolescents are included, but mean age at diagnosis was 42–50 y and no pediatric or adolescent subgroup analysis was performed. |
| Zeevi et al., 2015 [51] | Design: Prospective cohort with continuous glucose monitoring, followed by validation in an independent cohort and a blinded randomized controlled dietary intervention. Timing: Prospective cohort with a prospective, blinded, randomized controlled evaluation of the algorithm-guided diet—the only prospectively and interventionally evaluated model in Table 1. | Main cohort: 800 individuals with week-long continuous glucose monitoring and 46,898 meals recorded. Validation cohort: An independent 100-person cohort. Exact age range, sex distribution and BMI/obesity status not available. The cohort was not restricted to people with obesity or diabetes. | Development: 800-person cohort, 46,898 meals. Validation: Independent 100-person cohort, plus a blinded randomized controlled dietary intervention based on the algorithm’s predictions. Internal/external: Internal: Cross-validation (details not available from the paper). External: Independent 100-person cohort, plus prospective randomized interventional evaluation. | Postprandial glycemic response to real-life meals, measured by continuous glucose monitoring (a continuous physiological outcome, not a disease diagnosis). Reference standard: CGM-derived incremental glucose response. | Blood parameters, dietary habits, anthropometrics, physical activity and gut microbiome features. The complete predictor list is not available. | ML (gradient boosting regression) integrating the above data types. | Not applicable in the diagnostic sense—the model predicts a continuous outcome and is reported by correlation between predicted and measured postprandial responses. Exact R/R2 values are not available from the paper. | Not available | Not available | The approach was subsequently commercialized as a personalized nutrition service, but no regulated clinical decision-support deployment is reported in this paper. | None. Adult cohort; no pediatric data. |
3.2. Predictive Models for the Diagnosis and Management of MASLD
| Article | Study Design; Prospective or Retrospective | Population: Exact Age Range and Characteristics | Model-Development Sample; Validation Sample; Internal and External Validation | Outcome Definition and Reference Standard | Predictor Variables | Algorithm | Discrimination Metrics | Calibration | Interpretability/Explainability | Clinical Availability/Deployment Status | Pediatric Applicability |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Das et al., 2021 [81] | Design: Retrospective digital image analysis of de-identified hepatic ultrasound images obtained as part of a cross-sectional study of pediatric NAFLD prevalence (Valleywise Health Medical Center, Phoenix, AZ, USA). Timing: Retrospective analysis of images collected in a prior cross-sectional study. | Children. Development set: 93 subjects with normal liver and 39 with confirmed NAFLD (n = 132). External validation set: 42 children. Exact age range, sex distribution and BMI not available. | Development: Unit of analysis is the region of interest, not the patient: 484 ROIs from 93 normal subjects and 260 ROIs from 39 subjects with NAFLD (744 ROIs from 132 children), each with 28 extracted texture features, used to develop, train and internally validate the model. Validation: External validation cohort of 42 children contributing 211 ROIs. Internal/external: Internal: Development plus internal validation on the 132-child dataset. External: Independent cohort of 42 children (211 ROIs). | NAFLD versus normal liver. The paper states “confirmed NAFLD” but does NOT specify the reference standard (histology, MRI-PDFF, elastography or ultrasound reading). This is a critical unreported item. | 28 texture features extracted from a representative region of interest on hepatic ultrasound images using ImageJ and MAZDA image analysis software. Comparators: Hepatorenal index and hepatic echo-intensity attenuation index (pixel-intensity-based). | Ensemble ML model combining SVM, neural network and extreme gradient boosting. Multiple classification algorithms were evaluated. | Combined AUC for SVM, Multi-Layered Perceptron Neural Net and XGBoost 0.978 in the training set, 0.951 in the testing set, 0.969 in the validation set; AUC of 0.92 (95% CI, 0.91–0.94) when retesting in the external validation dataset. | Not reported | Hand-crafted texture features are inherently interpretable; no formal explainability method reported in the paper. | None. Research prototype. | Fully pediatric and the only pediatric imaging AI study in Table 2 with a separate external validation cohort. Ultrasound is widely available in pediatrics, which favors translation, but the age range and clinical characteristics of the children are not reported. |
| Wang et al., 2025 [82] | Design: Cross-sectional analysis of baseline data from the SCIENT cluster-randomized trial (ClinicalTrials.gov NCT05482165) conducted in six primary schools in Ningbo, China, September 2022 to June 2023. Timing: Cross-sectional analysis of prospectively collected trial baseline data. | 161 grade 3 children aged 8–10 years overweight or obese by Chinese national standards (median age 8.5 y, IQR 8.3–8.8); 58/161 (36%) girls. Median BMI z-score 2.10 (non-MASLD) versus 2.72 (MASLD). 42/161 (26.1%) had MASLD. Exclusions: Heart disease, hypertension, diabetes, asthma, viral hepatitis, nephritis, secondary or drug-induced obesity, abnormal development, inability to take part in school sports, recent induced weight loss. | Development: 161 children with 42 outcome events; five-fold stratified cross-validation used for sequential forward feature selection and AUC estimation. Six predictors in the final model, i.e., approximately 7 events per predictor. Validation: Internal replication only: random 2:1 train-test split (n = 107/54) and a school-based split (4 schools, n = 110, for training; 2 schools, n = 51, for testing). No independent external cohort; the authors acknowledge that external validation in larger pediatric cohorts is still required. Internal/external: Internal: Five-fold stratified CV, 2:1 random split, school-based split. External: None. | MASLD defined as hepatic steatosis on vibration-controlled transient elastography (FibroScan, CAP ≥ 248 dB/m; median of 10 valid measurements, results with IQR/median >30% discarded) plus at least one cardiometabolic risk factor, which all participants met by virtue of overweight or obesity. Fibrosis defined as LSM ≥ 7.0 kPa (present in 1/42). Reference standard: VCTE, not histology or MRI-PDFF. | 92 inflammation-related plasma proteins (Olink Explore 96 Inflammation panel, proximity extension assay); 82 retained after excluding proteins detected in <75% of samples; 20 significant on univariable analysis, 15 robust after adjustment for age, sex, BMI and school. Final six-protein ProScore panel: FGF-21, CDCP1, CD244, OPG, Flt3L, MCP-1. Comparators: 11 anthropometric/metabolic indices (WHtR, METS-IR, SPISE, PNFI, VAI, LAP, TyG, TyG-ALT, TyG-WC, TyG-WHtR, TyG-BMI) and a 9-SNP genetic risk score. | Six classifiers compared—logistic regression, RF, DT, SVM, XGBoost, LightGBM—with model-specific variable importance ranking followed by sequential forward feature selection. Logistic regression achieved the highest cross-validated AUC and was used to generate the ProScore (the published formula is a predicted probability). | Cross-validated AUC 0.836 Random 2:1 split test AUC 0.818; school-based split AUC 0.830. Sex-stratified: 0.907 (95% CI 0.830–0.984) in girls and 0.808 (0.717–0.898) in boys, DeLong p = 0.101. Stratified by genetic risk: 0.915 in the low-GRS group versus 0.800 in the high-GRS group, DeLong p = 0.003. Sensitivity analysis with CAP ≥ 270 dB/m: AUC 0.881 (0.807–0.955). Best comparator TyG-BMI 0.783; GRS 0.648. ProScore significantly exceeded every comparator (DeLong p < 0.05) and no combination improved on it. | Not assessed. No calibration plot, calibration slope or Brier score reported. | Model-specific variable importance (logistic and SVM coefficients, tree-based information gain), sequential forward selection, and GO/KEGG/Reactome pathway enrichment of the selected proteins. The final six-variable logistic model with a published formula is inherently interpretable. No SHAP or LIME. | None. The authors identify assay cost as a barrier and call for cross-platform validation using conventional assays (ELISA, targeted mass spectrometry) before translation. | High—fully pediatric (8–10 y) and restricted to children with overweight or obesity, exactly the target population of this review. Limitations for transfer: Very narrow age band, single Chinese city, pubertal status not assessed, VCTE reference standard, and dependence on a high-throughput proteomic platform that is not routinely available. |
| Li et al., 2025 [83] | Design: Cross-sectional single-center study, Department of Clinical Nutrition, Xi’an Children’s Hospital, Xi’an, China. Timing: Cross-sectional; timing of data collection relative to analysis not stated. | 219 children with obesity: 79 with MASLD and 140 without. Children with MASLD had higher weight (59.8 vs. 45.5 kg), BMI (28.03 vs. 24.56 kg/m2), waist circumference (82.64 vs. 69.30 cm), WHtR (0.54 vs. 0.49), body fat mass (26.06 vs. 18.13 kg), visceral fat area (123.89 vs. 85.06 cm2), ALT (40 vs. 19 U/L) and AST (32 vs. 26 U/L). Associations were stronger in boys and in children with obesity duration >3 years. | Development: 219 children with 79 events. Validation: Internal validation, bootstrap-corrected calibration plot. No external validation. | MASLD in children with obesity. | Demographic, anthropometric, body-composition and biochemical parameters. Top features: Weight, waist circumference, body fat mass and ALT. ALT was additionally modeled as a mediator, accounting for 32.9–38.3% of the adiposity-MASLD association. | Multivariable logistic regression, RF, LASSO regression, mediation models and a nomogram. | AUC 0.861 for the combined model of weight, waist circumference, body fat mass and ALT, described by the authors as outperforming single-metric approaches. | Reported as a bootstrap-corrected calibration plot This is one of only three studies across both tables that assessed calibration. | Nomogram for individual risk stratification, RF feature ranking and formal mediation analysis quantifying the role of ALT. | None. A nomogram is proposed for personalized risk stratification but no tool or software is reported. | High—fully pediatric and restricted to children with obesity. All predictors (weight, waist circumference, bioimpedance-derived fat mass, ALT) are routinely obtainable in pediatric practice, making this the most immediately translatable model in Table 2. Limited by the single-center design, modest sample and absence of external validation. |
| Zhan et al., 2025 [84] | Design: Cross-sectional metabolomic biomarker study with group-balanced sampling, plus in vitro mechanistic work in mouse hepatocytes and liver organoids. Discovery participants recruited during hospital visits (Children’s Hospital, Zhejiang University School of Medicine, Hangzhou); validation participants sampled from schools. Timing: Cross-sectional; samples collected prospectively, models fitted retrospectively. | Discovery set n = 110: 30 normal weight, 30 healthy obesity, 30 obesity with MASL, 20 obesity with MASH. Mean age 11.65 (SD 2.20) y across groups, with a male predominance. Obesity by the Chinese Standard for Overweight and Obesity among School-Age Children and Adolescents; severity stratified by BMI z-score (overweight 1 to <2, mild obesity 2 to <3, severe obesity ≥3). Exclusions: Type 1 diabetes, chronic liver disease other than MASLD, drugs causing steatosis within 12 months. Validation set n = 112 children with obesity (37 healthy obesity, 56 MASL, 19 MASH), stratified—randomly selected from 336 children with obesity at two primary schools and one middle school. | Development: MASL versus healthy obesity model: 60 children (30 vs. 30). MASH versus MASL model: 50 children (20 vs. 30). Very small development samples. Validation: Independent validation cohort of 112 children with obesity recruited in a different setting (schools rather than hospital)—a genuine external validation in terms of setting and sampling. Internal/external: Internal: Model development in the discovery set. External: Independent 112-child validation cohort. | Hepatic steatosis diagnosed by proton magnetic resonance spectroscopy (1H-MRS), FibroScan OR liver ultrasound, i.e., the reference standard differed between participants. MASH defined non-invasively as imaging-confirmed steatosis plus persistent serum ALT >60 U/L for more than 3 months in the absence of secondary causes. No liver biopsy, which the authors justify on ethical grounds in children. | Untargeted plasma metabolomics (731 metabolites across four UPLC-MS/MS methods) plus clinical parameters. Final MASL-versus-healthy-obesity model: tryptophan (TRP), N-acetyltryptophan (AcTRP) and quinolinic acid (QA). Final MASH-versus-MASL model: N-acetyl-L-methionine, oxoglutaric acid, taurocholic acid, cysteine-glutathione disulphide and glycocholic acid. | Logistic regression for the MASL model and a neural network for the MASH model. Supporting analyses: PCA and OPLS-DA for exploratory profiling, fuzzy c-means (mfuzz) clustering of metabolite trajectories, and SHAP for interpretation. | Discovery set, MASL versus healthy obesity—single metabolites TRP 0.750, AcTRP 0.792, QA 0.693, versus clinical comparators ALT 0.745, BMI 0.752, UA 0.746; combined three-metabolite logistic model AUC 0.874 with sensitivity 86.7%, specificity 67.7%, accuracy 76.7%. MASH versus MASL-AST 0.944 and GGT 0.938 (ALT excluded as it is part of the MASH definition), TRP 0.743; combined five-metabolite neural network AUC 0.847 with sensitivity 75.0%, specificity 76.7%, accuracy 76%. Validation set: Performance is described only as “replicated” and “maintained”, shown graphically); no numerical auc or confidence interval is given in the text for the validation cohort. | Not assessed. | SHAP analysis applied to the final models, identifying AcTRP, TRP and QA as the dominant contributors; supported by mechanistic in vitro experiments showing that these metabolites promote hepatocyte lipid accumulation via oxidative stress. | None. | High—fully pediatric (mean 11.65 y), obesity-specific, and the only study in Table 2 with a genuinely independent validation cohort recruited in a different setting. Translation is limited by dependence on untargeted UPLC-MS/MS metabolomics and by a heterogeneous imaging reference standard. |
| Zöggeler et al., 2025 [85] | Design: Systematic review (MOOSE) with pooled individual-level reanalysis of raw shotgun metagenomic sequencing data from nine published studies plus one newly recruited cohort (Medical University of Innsbruck), followed by development of ML classifiers on the pooled data. Timing: Retrospective pooling of previously published datasets plus one prospectively recruited cohort. | 413 children analyzed: 132 healthy controls, 58 with obesity, 153 with MASLD and 70 with MASH. Median ages—controls 9 y (IQR 5.7–12), obesity 13 y (9.6–14), MASLD 13 y (12–14.7; 62 missing), MASH 12 y (10–14). Median BMI—controls 16, obesity 30.2, MASLD 31.1, MASH 30.8. Female 45.5%, 46.6%, 31.8% and 24.3% respectively. Fibrosis in the MASH group: F0–F1 48.6%, F2 14.3%, F3–F4 8.6%, missing 28.6%. An additional adult MASLD cohort (n = 163) was included for pediatric-versus-adult comparison. | Development: Pooled pediatric data; group sizes vary by comparison (obesity n = 58 versus MASLD n = 153; MASLD n = 153 versus MASH n = 70), against hundreds of microbial species and metabolic pathway features. Validation: Internal only: 10-fold cross-validation with five repeats (R caret) and hyperparameter tuning. No external validation. Internal/external: Internal: Repeated 10-fold CV. External: None. | MASLD diagnosed by ultrasound, magnetic resonance imaging OR liver histology depending on the source study; MASH defined as additional biochemical OR biopsy-proven hepatic inflammation. Obesity defined as BMI at or above the 95th percentile. Studies including patients with T2DM were excluded. The reference standard therefore differs across participants. | Gut microbiome species abundance from shotgun metagenomic sequencing and MetaCyc metabolic pathway abundance (HUMAnN3), after MMUPHin batch-effect correction using study as the batch and disease state as a covariate. | RF and XGBoost (R caret), each with 10-fold cross-validation and five repeats and hyperparameter tuning; XGBoost shrinkage used to limit overfitting. Supporting analyses: Alpha and beta diversity, PERMANOVA, LEfSe/LDA, ALDEx2, MaAsLin2. | Taxonomy-based models—MASLD versus obesity: XGBoost AUROC 87% (95% CI 0.82–0.92), RF 85%; MASH versus MASLD: XGBoost and RF both 89% (0.84–0.94). Pathway-abundance models—MASLD versus obesity: XGBoost 81% (0.76–0.86), RF 79% (0.73–0.85); MASH versus MASLD: XGBoost 88% (0.83–0.93), RF 85% (0.79–0.91). Pediatric versus adult MASH: AUROC 97%. | Not assessed. | Ranked feature importance from both models, LEfSe/LDA differential abundance and pathway-level analyses identifying Faecalibacterium prausnitzii, Prevotella copri, Anaerobutyricum (Eubacterium) hallii, Romboutsia timonensis and Intestinibacter bartlettii, and the methanogenesis-from-acetate pathway. No SHAP. | None. Proposed as a potential fecal biomarker. | High in relevance—the largest pooled pediatric MASLD microbiome dataset available—but of limited practical applicability, since shotgun metagenomic sequencing is a research tool, the pooled cohorts span several countries and ethnicities, and the reference standard is heterogeneous. |
| Ji et al., 2022 [59] | Design: Cross-sectional targeted metabolomics study with ML, pooling participants from four parent studies at Gachon University Medical Center, Republic of Korea (healthy volunteers; an MR-based NAFLD study; a bariatric surgery cohort; and living liver transplant donors). Liver RNA sequencing performed in a subset. Timing: Retrospective pooled analysis of four parent studies. | 86 adults aged 19–70 years: 25 healthy controls (mean age 35.2 y), 42 with NAFL (43.2 y) and 19 with NASH (41 y). Exclusions: Alcohol >20 g/day (women) or >30 g/day (men), other liver or biliary disease, drugs causing secondary steatosis within one year. Not obesity-defined. NOTE: Section 2.8 of the paper refers to 89 participants while the rest of the paper reports 86—an internal inconsistency. | Development: Pairwise 75%/25% splits: healthy versus NAFL 51 training/16 test; healthy versus NASH 34/10; NAFL versus NASH 47/14. Extremely small. Validation: Internal only: 10-fold cross-validation and leave-one-out cross-validation plus the 25% hold-out. No external validation; the authors themselves state that validation of the MetaNASH score in independent cohorts is warranted. Internal/external: Internal: 10-fold CV, LOOCV, 75/25 split. External: None. | NASH defined as either NAFLD activity score ≥ 4 on liver biopsy OR MRI-PDFF ≥ 16.1% together with MR elastography liver stiffness ≥ 3.8 kPa in participants without biopsy; NAFL as MRI-PDFF ≥ 5%; healthy controls as MRI-PDFF <5% with normal liver enzymes and no biopsy. Only 12 of 86 participants underwent liver biopsy, so for most the reference standard was an MR-based algorithm previously derived by the same investigators—which the authors acknowledge as the study’s main limitation. | 79 plasma metabolites measured by GC-MS/MS and LC-MS/MS (amino acids, kynurenine pathway metabolites, nucleosides, organic acids, fatty acids). Eight selected by RF and multinomial logistic regression (glutamic acid, cis-aconitic acid, aspartic acid, isocitric acid, alpha-ketoglutaric acid, oxaloacetic acid, myristoleic acid, tyrosine); three retained by a recursive partitioning and regression tree (glutamic acid, isocitric acid, aspartic acid), combined into the MetaNASH score = log10(aspartic acid1 × isocitric acid2 × glutamic acid4). | RF (primary), multinomial logistic regression, recursive partitioning and regression tree, with PLS-DA for exploratory multivariate analysis. | RF classifiers—NAFL versus healthy controls (8 features) AUROC 0.900 (95% CI 0.854–0.947); NASH versus healthy controls all classifiers >0.960, best 0.990 with 4 features; NASH versus NAFL best 0.849 with 4 features. MetaNASH score for NASH discrimination: AUROC 0.877 at a cut-off of 4.55, computed in the WHOLE cohort WITHOUT any training/test separation, i.e., an apparent (optimistic) estimate. | Not assessed. | RF variable importance, an explicit DT, multinomial logistic regression coefficients, and integration of metabolomics with liver RNA-seq to build a metabolic map linking plasma metabolites to hepatic enzyme expression. The final MetaNASH score is a closed-form, fully transparent formula. | None. | None. Eligibility was restricted to ages 19–70 years; no pediatric data. |
| Noureddin et al., 2022 [60] | Design: Retrospective cross-sectional cohort analysis of the nationally representative NHANES 2017–2018 survey (United States). Timing: Retrospective analysis of cross-sectional survey data. | Adults aged ≥ 20 years with valid reproducible transient elastography (>10 measurements, IQR <30% of the median). From 5494 with a completed examination, 4471 met age and validity criteria; after excluding 640 with high alcohol consumption, viral hepatitis or HIV, 3831 entered the ML analysis (1226 with NAFLD, 2605 without). A T2DM subpopulation of 908 included 468 with NAFLD. Known over-representation of participants aged ≥ 60 y and of African American and Hispanic participants. Not obesity-selected. | Development: 2874 in the training set (75%), with 10-fold cross-validation and five replications for hyperparameter tuning. Over 100 candidate features. Validation: 957 in the internal test set (25%). No external validation. Internal/external: Internal: 75/25 split with 10-fold CV × 5 repeats. External: None. | NAFLD defined as controlled attenuation parameter ≥ 302 dB/m (Youden-optimal threshold) on FibroScan; fibrosis staged by VCTE liver stiffness (F0–F1 ≤ 8.2, F2 ≤ 9.7, F3 ≤ 13.6, F4 > 13.6 kPa). No participant had biopsy confirmation, and other causes of liver disease such as autoimmune hepatitis, primary biliary cholangitis and haemochromatosis could not be excluded; alcohol intake was self-reported and may be underestimated. Both limitations are acknowledged by the authors. | Over 100 features: demographics (age, race/ethnicity, sex, marital status, education), clinical characteristics (BMI, waist circumference, blood pressure), laboratory values (HbA1c, AST, ALT, alkaline phosphatase, bilirubin, HDL) and comorbidities (diabetes, hypertension). Significant predictors on logistic regression: male sex, HbA1c, age, BMI, waist circumference, AST, alkaline phosphatase, diastolic blood pressure and HDL. | Six models compared: Logistic regression, elastic net, conditional single-classification tree, RF, SVM and neural network. Logistic regression selected as the model of choice for simplicity and interpretability given equivalent performance. | Test-set AUROC: elastic net 0.84 (0.81–0.86), logistic regression 0.83 (0.81–0.86), RF 0.83 (0.80–0.86), SVM 0.83 (0.80–0.85), neural network 0.83 (0.80–0.85), classification tree 0.79 (0.76–0.82). Accuracy 0.75–0.79; sensitivity 0.52–0.71; specificity 0.78–0.90; PPV 0.60–0.72; NPV 0.80–0.85. | Not assessed. | Logistic regression and elastic net explicitly chosen as the “interpretable” model classes, with odds ratios reported for individual predictors. No SHAP or LIME. | None. Proposed for identifying candidates for further assessment across large datasets. | None. Adults aged ≥ 20 years, with over-representation of participants aged ≥ 60 y. |
| Razmpour et al., 2023 [61] | Design: Cross-sectional study with volunteer recruitment by advertisement on university clinic notice boards and by telephone or email, in Khorasan Razavi (east) and Hormozgan (south) provinces, Iran. Timing: Cross-sectional with prospective recruitment of volunteers; retrospective modeling. | 593 recruited, 80 excluded, 513 analyzed. The Methods state participants aged above 13 years, but Table 1 of the paper gives an age range of 9–74 years (mean 37.04, SD 15.44) and guardians consented for participants under 18, so a minority of children were included. Mean weight 77.26 (SD 17.31) kg; mean BMI 28.15 (SD 4.89) kg/m2, range 15–52; 13.3% diabetic. Sex reported as 240 male/273 female in the text but 238 male/270 female in Table 1 of the original paper (n = 508), an internal inconsistency with the stated 513. Not obesity-selected. Exclusions: Underlying liver disease, several drug classes, alcohol use more than twice weekly, cancer in the past year, surgery in the past 6 months, pregnancy. | Development: 513 participants split into train and test sets (proportions NOT stated); each classifier trained and evaluated 50 times with results averaged. Validation: Internal only. The authors state that future studies with larger samples could “allocate separate validation sets”, implying no dedicated held-out validation set. No external validation. Internal/external: Internal: repeated train/test evaluation over 50 runs. External: None. | Hepatic steatosis and fibrosis staged by transient elastography (FibroScan): steatosis grade 3 at CAP ≥ 292 dB/m; fibrosis F0 < 6.2, F1 6.2–7.6, F2 7.6–8.8, F3 8.8–11.8, F4 ≥ 11.8 kPa. Three labels modeled: fatty liver present versus absent, steatosis stage, fibrosis stage. No histological confirmation; the authors acknowledge that this is not the gold standard. | Body composition and anthropometric indices. Most important features for fatty liver: abdomen circumference (importance 0.061), waist circumference (0.061), trunk fat (0.056), chest circumference (0.054) and BMI (0.053); similar rankings for steatosis and fibrosis staging, with sex-specific analyses reported. | Eight classifiers compared in scikit-learn: k-nearest neighbors, SVM, radial basis function SVM, Gaussian process, RF, neural network, AdaBoost and naïve Bayes, with PCA for feature extraction. RF performed best. | RF—fatty liver (any stage): accuracy 0.82, AUC 0.84; steatosis stage: accuracy 0.52, AUC 0.69; fibrosis stage: accuracy 0.57, AUC 0.58. | Not assessed. | Feature importance values reported for each outcome and separately by sex. No SHAP or LIME. | None. Proposed as a low-cost screening decision-support approach for primary care and remote settings. | Minimal. Although the reported age range begins at 9 years and minors were enrolled with guardian consent, the mean age is 37 years and no pediatric subgroup analysis was performed. The current Limitations entry “non pediatric data included” is therefore not strictly accurate; the accurate statement is that a small unspecified number of minors were included without any pediatric-specific analysis. |
| Huang et al., 2023 [62] | Design: prospective 5-year cohort study (baseline health checkups in 2010, follow-up to 2015), Zhenhai Lianhua Hospital, Ningbo, China; reported in accordance with STROBE. The only prospectively designed model-development study in either table. Timing: prospective cohort with 5-year follow-up. | From 17,611 attendees of the 2010 annual health checkup, 6196 adults without NAFLD were enrolled after excluding those without liver ultrasound, with existing liver disease, with alcohol intake >140 g/week (men) or >70 g/week (women), or lost to follow-up. Incident NAFLD occurred in 1155 (18.64%) over 5 years, of whom 941 (81.5%) were men. Among incident cases, 434 (37.6%) were lean (BMI < 24), 603 (52.2%) overweight (24 to <28) and 118 (10.2%) obese (≥28 kg/m2)—i.e., the cohort is NOT obesity-selected and most incident cases were not obese. | Development: Training and internal validation split 7:3; 10-fold cross-validation within the training set; hyperparameter optimization; SMOTE applied for class imbalance. 11 predictors selected, with the authors stating explicit compliance with the 10-events-per-variable rule. Validation: Internal validation set (30% split) and an external validation set consisting of the 2015–2020 follow-up population—a temporal external validation at the same center. Internal/external: Internal: 7:3 split plus 10-fold CV. External: Temporal external validation using the 2015–2020 follow-up population. | Incident NAFLD over 5 years, diagnosed on abdominal ultrasound (Toshiba Medical Systems) read independently by experienced ultrasonographers, with exclusion of excessive alcohol intake and other etiologies. No histological confirmation; the authors list ultrasound-based diagnosis as their first limitation. | 11 characteristic predictors screened by XGBoost recursive feature elimination combined with LASSO. The published nomogram uses age, BMI, waist circumference, white blood cell count, red blood cell count, ALT, gamma-glutamyl transpeptidase, uric acid, triglycerides, HDL and apolipoprotein-B. Restricted cubic splines used to characterize dose–response relationships. | Six models compared: Logistic regression, DT, SVM, RF, CatBoost and XGBoost. Logistic regression selected as the final model. | Training set (10-fold CV): CatBoost AUROC 0.810 (95% CI 0.768–0.852), RF 0.800 (0.762–0.838). Internal validation: Logistic regression 0.778 (0.759–0.794). EXTERNAL validation: Logistic regression 0.806 (0.788–0.821), with accuracy 0.801, precision 0.766, F1 0.648 and recall 0.628. | Asessed-calibration curves and Brier scores reported for both the internal and external validation sets; XGBoost showed the best calibration (Brier score 0.181 internally and 0.191 externally). One of only three studies in the whole review to report calibration. | Dynamic nomogram with a worked individual example, logistic regression coefficients, restricted cubic splines, and transparent XGBoost-RFE plus LASSO feature screening. The final model is inherently interpretable. No SHAP. | A web-based risk calculator was developed and published to support clinical use—the only model in either table with a publicly deployed tool. It is not reported as a regulated medical device and has not undergone prospective impact evaluation. | None. Adult health-checkup population; the authors note that applicability to other ethnic groups also remains unvalidated. |
| Qin et al., 2023 [63] | Design: Cross-sectional diagnostic/screening study using electronic medical record data from attendees of the annual health examination at Guilin People’s Hospital, China, January to December 2021. Timing: Retrospective analysis of a cross-sectional health examination dataset. | 14,439 adults aged ≥ 18 years: 4411 with NAFLD (30.5%) and 10,028 without. NAFLD group mean age 48.4 (SD 13.4) y, 76.6% male, mean BMI 27.2 (SD 3.2); non-NAFLD group 45.9 (14.8) y, 53.8% male, BMI 23.5 (3.0). Exclusions: alcohol > 210 g/week (men) or >140 g/week (women); viral, autoimmune or drug-induced liver disease and other chronic or secondary liver disease; acute or chronic infection; pregnancy or lactation; psychiatric disorders; malignancy. Not obesity-selected. | Development: Random 7:3 split, approximately 10,107 in the training set. Grid search with 10-fold cross-validation for hyperparameters. z-score standardization fitted on the training set and applied unchanged to the test set. Validation: Internal only: Approximately 4332 in the test set. No external validation. Internal/external: Internal: 7:3 split with grid search and 10-fold CV. External: None. | NAFLD diagnosed by color Doppler ultrasound (GE LOGIQ, 3.5 MHz probe) by operators with at least 5 years of experience, with secondary causes excluded. No histological confirmation. | Age, sex, BMI, systolic and diastolic blood pressure, complete blood count, liver function panel (bilirubins, ALT, AST, AST/ALT ratio, GGT, ALP, total protein, albumin, globulin, albumin/globulin ratio) and lipid panel (triglycerides, total cholesterol, HDL, LDL, VLDL), all drawn from the electronic medical record. Most important features across the tree-based models: BMI, triglycerides, ALT and the AST/ALT ratio (plus VLDL-C for RF). | DT (CART, gini), RF, XGBoost and SVM, implemented in Python/scikit-learn. | Test set—SVM: accuracy 0.801, PPV 0.795, F1 0.795, kappa 0.508, AUPRC 0.712, AUROC 0.850; RF: AUROC 0.852 (the highest of any model), accuracy 0.789, PPV 0.782, F1 0.782, kappa 0.478, AUPRC 0.708; XGBoost: AUROC 0.833, accuracy 0.781; DT: AUROC 0.820, accuracy 0.765. All with 95% confidence intervals. The SVM AUROC is 0.850. | Not assessed. | Feature importance reported for every classifier, including an explicit DT structure and XGBoost gain rankings. The authors deliberately favored a small predictor set to keep the tool usable in primary care. No SHAP. | None. Proposed as a screening aid for physicians and primary care doctors. | None. Adults aged ≥ 18 years. |
| Rhyou and Yoo, 2021 [73] | Design: Retrospective deep learning image classification study on B-mode liver ultrasound images. The unit of analysis is the IMAGE, not the patient. Timing: Retrospective. | The number of individual patients, their age, sex, BMI, obesity status, indication for scanning and clinical setting are all absent. Images were pooled from two sources: a Samsung ACUSON Sequoia 512 dataset and the publicly available Byra dataset acquired on a GE Vivid E9. | Development: Ultrasound images split 6:2:2 into training, validation and test sets at the IMAGE level. Class labels: normal, mild, moderate, severe steatosis. Validation: Internal validation and test partitions of the same pooled image dataset. No external validation—the public Byra dataset was merged into the training/validation/test pool rather than held out as an independent test set. Internal/external: Internal: 6:2:2 image-level split. External: None. | Steatosis grade (normal, mild, moderate, severe) as previously annotated by medical experts on the ultrasound images. The reference standard is therefore expert visual reading of the SAME image supplied to the model; no histology, MRI-PDFF or biochemical confirmation. The number of readers, their independence and inter-reader agreement are not reported. | Ultrasound image pixel data from the liver–kidney region, after resizing to 960 × 720 px, removal of metadata and black borders, and histogram equalization. | Cascade of three deep neural networks: DeepLabv3+ with transfer learning for semantic segmentation of the liver–kidney area; Inception v3 (transfer-learned) for classifying parasagittal versus non-parasagittal images and for ring detection; and SteatosisNet for grading disease severity. | Sensitivity 99.78%, specificity 100%, PPV 100%, NPV 99.83%, diagnostic accuracy 99.91%; parasagittal detection accuracy 99.90%. No confidence intervals. These values are implausibly high for ultrasound-based steatosis assessment and are characteristic of image-level rather than patient-level data partitioning. | Not assessed. | Segmentation masks and cropped regions of interest can be visually inspected, providing a degree of transparency about which anatomy drives the prediction. No formal explainability method. | None. | None, and not assessable—no patient ages are reported anywhere in the paper. Pediatric liver ultrasound differs in acquisition and in normal appearances, so transfer to children cannot be assumed. |
| Zhou et al., 2025 [67] | Design: Cross-sectional analysis of NHANES 2017–2018 using the survey’s stratified multistage probability design with sampling weights applied throughout. Timing: Retrospective analysis of cross-sectional survey data. | From 9254 initial participants, 3306 were excluded for missing controlled attenuation parameter data and 894 for not meeting MASLD diagnostic eligibility, leaving 5054 US adults aged ≥ 18 years. Median age by visceral adiposity index tertile 44, 47 and 50 years; median BMI 25.9, 28.7 and 31.3 kg/m2; sex distribution balanced. Not obesity-selected. | Development: Stratified 7:3 training/test split; 11 predictors selected by LASSO regression with 10-fold cross-validation using the lambda.1se criterion. Validation: Internal only (30% test partition). No external validation. Internal/external: Internal: Stratified 7:3 split with LASSO/10-fold CV for predictor selection. External: None. | MASLD defined by controlled attenuation parameter-based hepatic steatosis on transient elastography together with cardiometabolic criteria. No histological confirmation. | 11 LASSO-selected predictors: visceral adiposity index, marital status, hypertension, diabetes, sex, age, race, platelet count, albumin, AST and ALT. Comparators: Seven established non-invasive scores. | Eight ML models compared (RF, SVM, generalized linear model, gradient boosting machine, k-nearest neighbors, neural network, DT) plus a nomogram. | RF AUC 0.869, gradient boosting machine 0.868, generalized linear model 0.852, neural network 0.504 (i.e., no better than chance, unexplained). Non-invasive scores: lipid accumulation product 0.834, fatty liver index 0.833, hepatic steatosis index 0.799, visceral adiposity index 0.736, TyG index 0.732, NAFLD fibrosis score 0.606, FIB-4 0.553. VAI itself showed a strong dose–response association with MASLD (adjusted OR for tertile 3 versus 1: 7.08, 95% CI 4.35–11.5; p for trend 0.003). The authors’ own conclusion is that the simple LAP and FLI scores, not the machine learning models, offer the best balance of accuracy and clinical practicality. | Not reported. A nomogram is presented without an accompanying calibration curve. | LASSO-selected predictor set, a nomogram, and explicit benchmarking against seven interpretable clinical scores. No SHAP. | None. The authors explicitly note that ML models face translational barriers from algorithmic complexity and resource demands, whereas LAP and FLI provide immediate clinical utility. | None. Adults aged ≥ 18 years. |
3.3. Limitations
4. Discussion
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| T2DM | Type 2 Diabetes Mellitus |
| MASLD | Metabolic Dysfunction-Associated Steatotic Liver Disease |
| AI | Artificial Intelligence |
| ML | Machine Learning |
| SNPs | Single Nucleotide Polimorphisms |
| WHO | World Health Organization |
| BMI | Body Mass Index |
| COVID-19 | Coronavirus Disease 2019 |
| GWASs | Genome-Wide Association Studies |
| PYY | Peptide YY |
| GLP-1 | Glucagon-Like Peptide-1 |
| OXM | Oxintomodulin |
| CCK | Cholecystokinin |
| GIP | Gastric Inhibitory Polypeptide |
| PP | Pancreatic Polypeptide |
| OSAS | Obstructive Sleep Apnea Syndrome |
| BED | Binge Eating Disorder |
| MS | Metabolic Syndrome |
| MASH | Metabolic-Associated Steatohepatitis |
| DL | Deep Learning |
| NLP | Natural Language Processing |
| PCA | Principal Component Analysis |
| SVM | Support Vector Machine |
| ANN | Artificial Neural Network |
| CV | Computer Vision |
| CNNs | Convolutional Neural Networks |
| RNNs | Recurrent Neural Networks |
| EHRs | Electronic Health Records |
| NGS | Next-Generation Sequencing |
| CHICA | Child Health Improvement via Computer Automation |
| AAP | American Academy of Pediatrics |
| LLMs | Large Language Models |
| DTx | Digital Treatments |
| IOT | Internet of Things |
| NB | Naïve Bayes |
| DTs | Decision Trees |
| RF | Random Forest |
| KNN | K-Nearest Neighbor |
| LR | Logistic Regression |
| GB | Gradient Boosting |
| HDL | High-Density Lipoprotein |
| CART | Classification and Regression Tree |
| LASSO | Least Absolute Shrinkage and Selection Operator |
| XGBoost | eXtreme Gradient Boosting |
References
- Valerio, G.; Maffeis, C.; Saggese, G.; Ambruzzi, M.A.; Balsamo, A.; Bellone, S.; Bergamini, M.; Bernasconi, S.; Bona, G.; Calcaterra, V.; et al. Diagnosis, treatment and prevention of pediatric obesity: Consensus position statement of the Italian Society for Pediatric Endocrinology and Diabetology and the Italian Society of Pediatrics. Ital. J. Pediatr. 2018, 44, 88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Levels and Trends in Child Malnutrition: UNICEF/WHO/World Bank Group Joint Child Malnutrition Estimates: Key Findings of the 2023 Edition; World Health Organization: Geneva, Switzerland, 2023. [Google Scholar]
- Littleton, S.H.; Berkowitz, R.I.; Grant, S.F.A. Genetic Determinants of Childhood Obesity. Mol. Diagn. Ther. 2020, 24, 653–663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Panera, N.; Mandato, C.; Crudele, A.; Bertrando, S.; Vajro, P.; Alisi, A. Genetics, epigenetics and transgenerational transmission of obesity in children. Front. Endocrinol. 2022, 13, 1006008. [Google Scholar]
- Alfano, R.; Robinson, O.; Handakas, E.; Nawrot, T.S.; Vineis, P.; Plusquin, M. Perspectives and challenges of epigenetic determinants of childhood obesity: A systematic review. Obes. Rev. 2022, 23, e13389. [Google Scholar] [PubMed]
- Koliaki, C.; Liatis, S.; Dalamaga, M.; Kokkinos, A. The Implication of Gut Hormones in the Regulation of Energy Homeostasis and Their Role in the Pathophysiology of Obesity. Curr. Obes. Rep. 2020, 9, 255–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obradovic, M.; Sudar-Milovanovic, E.; Soskic, S.; Essack, M.; Arya, S.; Stewart, A.J.; Gojobori, T. Isenovic ER Leptin and Obesity: Role and Clinical Implication. Front. Endocrinol. 2021, 12, 585887. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maqsood, S.; Ahmed, F.; Arshad, M.T.; Ikram, A.; Abdullahi, M.A. Comparative Analysis of Food Addiction and Obesity: A Critical Review. Food Sci. Nutr. 2025, 13, e70799. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nogueira-de-Almeida, C.A.; Weffort, V.R.S.; Ued, F.d.V.; Ferraz, I.S.; Contini, A.A.; Martinez, E.Z.; Del Ciampo, L.A. What causes obesity in children and adolescents? J. Pediatr. 2024, 100, S48–S56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Subramanian, M.; Wojtusciszyn, A.; Favre, L.; Boughorbel, S.; Shan, J.; Letaief, K.B.; Pitteloud, N.; Chouchane, L. Precision medicine in the era of artificial intelligence: Implications in chronic disease management. J. Transl. Med. 2020, 18, 472. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salama, M.; Balagopal, B.; Fennoy, I.; Kumar, S. Childhood Obesity, Diabetes. and Cardiovascular Disease Risk. J. Clin. Endocrinol. Metab. 2023, 108, 3051–3066, Erratum in J. Clin. Endocrinol. Metab. 2024, 109, e1422. https://doi.org/10.1210/clinem/dgae030. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Srinivasan, S.; Chen, L.; Todd, J.; Divers, J.; Gidding, S.; Chernausek, S.; Gubitosi-Klug, R.A.; Kelsey, M.M.; Shah, R.; Black, M.H.; et al. The first genome-wide association study for type 2 diabetes in youth: The Progress in Diabetes Genetics in Youth (ProDiGY) Consortium. Diabetes 2021, 70, 996–1005. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, S.; Kelly, A.S. Review of Childhood Obesity: From epidemiology, etiology, and comorbidities to clinical assessment and treatment. Mayo Clin. Proc. 2017, 92, 251–265. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DeBoer, M.D. Assessing and Managing the Metabolic Syndrome in Children and Adolescents. Nutrients 2019, 11, 1788. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zong, X.; Bovet, P.; Xi, B. A Proposal to Unify the Definition of the Metabolic Syndrome in Children and Adolescents. Front. Endocrinol. 2022, 13, 925976. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stroes, A.R.; Vos, M.; Benninga, M.A.; Koot, B.G.P. Pediatric MASLD: Current understanding and practical approach. Eur. J. Pediatr. 2024, 184, 29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mukherjee, J.; Sharma, R.; Dutta, P.; Bhunia, B. Artificial intelligence in healthcare: A mastery. Biotechnol. Genet. Eng. Rev. 2024, 40, 1659–1708. [Google Scholar] [PubMed]
- Jiang, F.; Jiang, Y.; Zhi, H.; Dong, Y.; Li, H.; Ma, S.; Wang, Y.; Dong, Q.; Shen, H.; Wang, Y. Artificial intelligence in healthcare: Past, present and future. Stroke Vasc. Neurol. 2017, 2, e000101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Esteva, A.; Robicquet, A.; Ramsundar, B.; Kuleshov, V.; DePristo, M.; Chou, K.; Cui, C.; Corrado, G.; Thrun, S.; Dean, J. A guide to deep learning in healthcare. Nat. Med. 2019, 25, 24–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, H.; Hwang, J.; Yon, D.K.; Rhee, S.Y. Multimodal and Multidimensional Artificial Intelligence Technology in Obesity. JOMES 2025, 34, 394–404. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peng, K.; Peng, Z.; Zhang, R. “Enhancing Neighborhood Food Availability for Safer and Healthier Urban Environments: A Cross-Sectional Investigation in Changsha, China,” in Designing Healthy Buildings and Communities: Shaping a Climate-Resilient Future; Chesmehzangi, A., Zuo, J., Sharifi, A., Zhang, R., Bafarasat, A.Z., Zhao, J., Eds.; Springer: Berlin/Heidelberg, Germany, 2025; pp. 99–123. [Google Scholar]
- Osadchiy, V.; Bal, R.; Mayer, E.A.; Kunapuli, R.; Dong, T.; Vora, P.; Petrasek, D.; Liu, C.; Stains, J.; Gupta, A. Machine learning model to predict obesity using gut metabolite and brain microstructure data. Sci. Rep. 2023, 13, 5488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tregellas, J.R.; Wylie, K.P.; Rojas, D.C.; Tanabe, J.; Martin, J.; Kronberg, E.; Cordes, D.; Cornier, M. Altered default network activity in obesity. Obesity 2011, 19, 2316–2321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ridaura, V.K.; Faith, J.J.; Rey, F.E.; Cheng, J.; Duncan, A.E.; Kau, A.L.; Griffin, N.W.; Lombard, V.; Henrissat, B.; Bain, J.R.; et al. Gut microbiota from twins discordant for obesity modulate metabolism in mice. Science 2013, 341, 1241214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singer, P.; Robinson, E.; Raphaeli, O. The future of artificial intelligence in clinical nutrition. Curr. Opin. Clin. Nutr. Metab. Care 2024, 27, 200–206. [Google Scholar] [PubMed]
- Wang, M.H. Artificial Intelligence Across the Obesity Continuum: From Mechanistic Insights to Global Precision Prevention and Therapy. Obesity 2026, 34, 294–316. [Google Scholar] [PubMed]
- Jafarabadi, G.S.; Busetto, L. Artificial Intelligence in Obesity Prevention. Healthcare 2025, 13, 3262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Azmi, S.; Kunnathodi, F.; Alotaibi, H.F.; Alhazzani, W.; Mustafa, M.; Ahmad, I.; Anvarbatcha, R.; Lytras, M.D.; Arafat, A.A. Harnessing Artificial Intelligence in Obesity Research and Management: A Comprehensive Review. Diagnostics 2025, 15, 396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, H.Y.; Chang, S.C.; Lin, W.Y.; Chen, C.H.; Chiang, S.H.; Huang, K.Y.; Chu, B.Y.; Lu, J.J.; Lee, T.Y. Machine Learning-Based Method for Obesity Risk Evaluation Using Single-Nucleotide Polymorphisms Derived from Next-Generation Sequencing. J. Comput. Biol. 2018, 25, 1347–1360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allen, B.; Lane, M.; Steeves, E.A.; Raynor, H. Using Explainable Artificial Intelligence to Discover Interactions in an Ecological Model for Obesity. Int. J. Environ. Res. Public Heal. 2022, 19, 9447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaur, R.; Kumar, R.; Gupta, M. Predicting risk of obesity and meal planning to reduce the obese in adulthood using artificial intelligence. Endocrine 2022, 78, 458–469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, J.; Liu, Z.; Liu, C.; Sun, H.; Li, X.; Yang, Y. Integrating Artificial Intelligence in the Diagnosis and Management of Metabolic Syndrome: A Comprehensive Review. Diabetes Metab. Res. Rev. 2025, 41, e70039. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, Y.A.; Huang, Y.; Dai, H.; Yuce, T.K.; Shah, V.; Bian, J.; Guo, J. Characterize Disease Progression Subphenotypes in Real World Populations with Overweight and Obesity using a Graph-based Neural Network Framework. medRxiv 2025. [Google Scholar] [CrossRef] [Scilit]
- Huang, L.; Huhulea, E.N.; Abraham, E.; Bienenstock, R.; Aifuwa, E.; Hirani, R.; Schulhof, A.; Tiwari, R.K.; Etienne, M. The Role of Artificial Intelligence in Obesity Risk Prediction and Management: Approaches, Insights, and Recommendations. Medicina 2025, 61, 358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, Z.; Berry, M.P.; Chwyl, C.; Hsieh, G.; Wei, J.; Forman, E.M. Comparing Large Language Model AI and Human-Generated Coaching Messages for Behavioral Weight Loss. J. Technol. Behav. Sci. 2025, 10, 749–760. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Machorro-Cano, I.; Alor-Hernández, G.; Paredes-Valverde, M.A.; Ramos-Deonati, U.; Sánchez-Cervantes, J.L.; Rodríguez-Mazahua, L. PISIoT: A Machine Learning and IoT-Based Smart Health Platform for Overweight and Obesity Management. Appl. Sci. 2019, 9, 3037. [Google Scholar] [CrossRef] [Scilit]
- Vazquez-Briseno, M.; Navarro-Cota, C.; Nieto-Hipólito, J.; Jiménez-García, E.; Sanchez-Lopez, J. A proposal for using the internet of things concept to increase children’s health awareness. In Proceedings of the CONIELECOMP 2012, 22nd International Conference on Electrical Communications and Computers, Cholula, Mexico, 27–29 February 2012; pp. 168–172. [Google Scholar]
- Zaragozá, I.; Guixeres, J.; Alcañiz, M.; Cebolla, A.; Saiz, J.; Álvarez, J. Ubiquitous monitoring and assessment of childhood obesity. Pers. Ubiquit. Comput. 2013, 17, 1147–1157. [Google Scholar]
- Hampl, S.E.; Hassink, S.G.; Skinner, A.C.; Armstrong, S.C.; Barlow, S.E.; Bolling, C.F.; Edwards, K.C.A.; Eneli, I.; Hamre, R.; Joseph, M.M.; et al. Clinical Practice Guideline for the Evaluation and Treatment of Children and Adolescents With Obesity. Pediatrics 2023, 151, e2022060640. [Google Scholar] [CrossRef] [PubMed]
- Zou, Q.; Qu, K.; Luo, Y.; Yin, D.; Ju, Y.; Tang, H. Predicting Diabetes Mellitus With Machine Learning Techniques. Front. Genet. 2018, 9, 515. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.-X.; Liu, Y.; Huang, R.; Wu, H.-Y.; Wang, Y.-Y.; Cao, S.-Y.; Wang, G.-Y.; Zhang, J.-M.; Ai, Z.-S.; Zhou, H.-M. Development and internal validation of a machine learning algorithm for the risk of type 2 diabetes mellitus in children with obesity. Front. Endocrinol. 2025, 16, 1649988. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, H.; Zhu, L.; Wang, P.; Yuan, K.; Nawrin, S.S.; Cui, Y.; Li, L. Dietary patterns and obesity are associated with type 2 diabetes risk in elderly Chinese men: A machine learning approach. Front. Nutr. 2025, 12, 1705683. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nomura, A.; Noguchi, M.; Kometani, M.; Furukawa, K.; Yoneda, T. Artificial Intelligence in Current Diabetes Management and Prediction. Curr. Diab. Rep. 2021, 21, 61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cardozo, G.; Pintarelli, G.B.; Andreis, G.R.; Lopes, A.C.W.; Marques, J.L.B. Use of Machine Learning and Routine Laboratory Tests for Diabetes Mellitus Screening. BioMed Res. Int. 2022, 2022, 8114049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, D.D.; Hu, F.B. Precision nutrition for prevention and management of type 2 diabetes. Lancet Diabetes Endocrinol. 2018, 6, 416–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Toro-Martin, J.; Arsenault, B.J.; Després, J.P.; Vohl, M.C. Precision nutrition: A review of personalized nutritional approaches for the prevention and management of metabolic syndrome. Nutrients 2017, 9, 913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Jin, N.; Zhan, Q.; Huang, Y.; Sun, A.; Yin, F.; Li, Z.; Hu, J.; Liu, Z. Machine learning-based risk predictive models for diabetic kidney disease in type 2 diabetes mellitus patients: A systematic review and meta-analysis. Front. Endocrinol. 2025, 16, 1495306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahlqvist, E.; Storm, P.; Käräjämäki, A.; Martinell, M.; Dorkhan, M.; Carlsson, A.; Vikman, P.; Prasad, R.B.; Aly, D.M.; Almgren, P.; et al. Novel subgroups of adult-onset diabetes and their association with outcomes: A data-driven cluster analysis of six variables. Lancet Diabetes Endocrinol. 2018, 6, 361–369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anjana, R.M.; Baskar, V.; Nair, A.T.N.; Jebarani, S.; Siddiqui, M.K.; Pradeepa, R.; Unnikrishnan, R.; Palmer, C.; Pearson, E.; Mohan, V. Novel subgroups of type 2 diabetes and their association with microvascular outcomes in an Asian Indian population: A data-driven cluster analysis: The INSPIRED study. BMJ Open Diab Res. Care 2020, 8, e001506. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, X.; Wu, C.; Yang, Y.; Su, W.; Dao, F.; Huang, J.; Shi, Z.; Lyu, H.; Lin, H. Interpretable machine learning-guided single-cell mapping deciphers multi-lineage pancreatic dysregulation in type 2 diabetes. Cardiovasc Diabetol. 2025, 24, 300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zeevi, D.; Korem, T.; Zmora, N.; Israeli, D.; Rothschild, D.; Weinberger, A.; Ben-Yacov, O.; Lador, D.; Avnit-Sagi, T.; Lotan-Pompan, M.; et al. Personalized nutrition by prediction of glycemic responses. Cell 2015, 163, 1079–1094. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mistry, S.; Riches, N.O.; Gouripeddi, R.; Facelli, J.C. Environmental exposures in machine learning and data mining approaches to diabetes etiology: A scoping review. Artif. Intell. Med. 2023, 135, 102461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mendes-Soares, H.; Raveh-Sadka, T.; Azulay, S.; Ben-Shlomo, Y.; Cohen, Y.; Ofek, T.; Stevens, J.; Bachrach, D.; Kashyap, P.; Segal, L.; et al. Model of personalized postprandial glycemic response to food developed for an Israeli cohort predicts responses in Midwestern American individuals. Am. J. Clin. Nutr. 2019, 110, 63–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mendes-Soares, H.; Raveh-Sadka, T.; Azulay, S.; Edens, K.; Ben-Shlomo, Y.; Cohen, Y.; Ofek, T.; Bachrach, D.; Stevens, J.; Colibaseanu, D.; et al. Assessment of a personalized approach to predicting postprandial glycemic responses to food among individuals without diabetes. JAMA Netw. Open 2019, 2, e188102. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lou, J.J.; Zeng, J. Artificial intelligence applications for managing metabolic dysfunction-associated steatotic liver disease: Current status and future prospects. World J. Gastroenterol. 2025, 31, 111900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.; Chen, Y.; Xiao, H.; Cai, J.; Wang, R.; Zeng, X.; Lin, M.; Liu, W.; Chi, X.; Chen, Q. Metabolomics-guided machine learning reveals diagnostic and mechanistic biomarkers in CHB with MASLD. PLoS ONE 2026, 21, e0331529. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, C.H.; Hsieh, Y.R.; Huang, S.Y.; Wang, W.; Chang, C.W.; Panunggal, B.; Chang, I.W.; Chen, C.L.; Chang, C.C.; Kao, W.Y. Serum Lipidome as a Predictor of Significant Liver Fibrosis in Patients with Severe Obesity Undergoing Bariatric Surgery. Obes. Surg. 2026, 36, 652–665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, F.; Sun, X.; Jiang, K.; Zhang, M.; Sun, C. Recent Advances in the Application of Machine Learning Models in Metabolic Dysfunction–Associated Steatotic Liver Disease. Diabetes/Metabolism Res. Rev. 2026, 42, e70129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ji, M.; Jo, Y.; Choi, S.J.; Kim, S.M.; Kim, K.K.; Oh, B.-C.; Ryu, D.; Paik, M.-J.; Lee, D.H. Plasma Metabolomics and Machine Learning-Driven Novel Diagnostic Signature for Non-Alcoholic Steato-hepatitis. Biomedicines 2022, 10, 1669. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Noureddin, M.; Ntanios, F.; Malhotra, D.; Hoover, K.; Emir, B.; McLeod, E.; Alkhouri, N. Predicting NAFLD Prevalence in the United States Using National Health and Nutrition Examination Survey 2017–2018 Transient Elastography Data and Application of Machine Learning. Hepatol. Commun. 2022, 6, 1537–1548. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Razmpour, F.; Daryabeygi-Khotbehsara, R.; Soleimani, D.; Asgharnezhad, H.; Shamsi, A.; Bajestani, G.S.; Nematy, M.; Pour, M.R.; Maddison, R.; Islam, S.M.S. Application of Machine Learning in Predicting Non-Alcoholic Fatty Liver Disease Using Anthropometric and Body Composition Indices. Sci. Rep. 2023, 13, 4942. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, G.; Jin, Q.; Mao, Y. Predicting the 5-Year Risk of Nonalcoholic Fatty Liver Disease Using Machine Learning Models: Prospective Cohort Study. J. Med. Internet Res. 2023, 25, e46891. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qin, S.; Hou, X.; Wen, Y.; Wang, C.; Tan, X.; Tian, H.; Ao, Q.; Li, J.; Chu, S. Machine Learning Classifiers for Screening Nonalcoholic Fatty Liver Disease in General Adults. Sci. Rep. 2023, 13, 3638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sorino, P.; Caruso, M.G.; Misciagna, G.; Bonfiglio, C.; Campanella, A.; Mirizzi, A.; Franco, I.; Bianco, A.; Buongiorno, C.; Liuzzi, R.; et al. Selecting the Best Machine Learning Algorithm to Support the Diagnosis of Non-Alcoholic Fatty Liver Disease: A Meta Learner Study. PLoS ONE 2020, 15, e0240867. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Y.; Liu, X.; Zhang, X.; Fei, Y.; Li, X. Machine learning-based prediction of metabolic dysfunction-associated steatotic liver disease using National Health and Nutrition Examination Survey (NHANES) data. PLoS ONE 2025, 20, e0335656. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, X.; Liu, S.; Zhao, Q.; An, M.; Hou, C.; Hu, S.; Niu, Y. Combining body roundness index and triglyceride-glucose index to enhance MASLD prediction: Insights from NHANES and machine learning. Hormones 2025, 25, 161–171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, T.; Ding, X.; Chen, L.; Huang, Q.; He, L. Visceral adiposity index as a predictor of metabolic dysfunction-associated steatotic liver disease: A cross-sectional study. BMC Gastroenterol. 2025, 25, 326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, X.; Zhang, T.; Park, S. Dietary quality, perceived health, and psychological status as key risk factors for newly developed metabolic dysfunction-associated steatotic liver disease in a longitudinal study. Nutrition 2025, 130, 112604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tavaglione, F.; Marafioti, G.; Romeo, S.; Jamialahmadi, O. Machine Learning Reveals the Contribution of Lipoproteins to Liver Triglyceride Content and Inflammation. J. Clin. Endocrinol. Metab. 2024, 110, 218–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verma, N.; Duseja, A.; Mehta, M.; De, A.; Lin, H.; Wong, V.W.; Wong, G.L.; Rajaram, R.B.; Chan, W.K.; Mahadeva, S.; et al. Machine learning improves the prediction of significant fibrosis in Asian patients with metabolic dysfunction-associated steatotic liver disease—The Gut and Obesity in Asia (GO-ASIA) Study. Food Pharmacol. Ther. 2024, 59, 774–788. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gil-Rojas, S.; Suárez, M.; Martínez-Blanco, P.; Torres, A.M.; Martínez-García, N.; Blasco, P.; Torralba, M.; Mateo, J. Prognostic Impact of Metabolic Syndrome and Steatotic Liver Disease in Hepatocellular Carcinoma Using Machine Learning Techniques. Metabolites 2024, 14, 305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shibata, N.; Morita, Y.; Ito, T.; Kanzaki, Y.; Watanabe, N.; Yoshioka, N.; Arao, Y.; Yasuda, S.; Koshiyama, Y.; Toyoda, H.; et al. A machine learning algorithm for stratification of risk of cardiovascular disease in metabolic dysfunction-associated steatotic liver disease. Eur. J. Intern Med. 2024, 129, 62–70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rhyou, S.Y.; Yoo, J.C. Cascaded Deep Learning Neural Network for Automated Liver Steatosis Diagnosis Using Ultrasound Images. Sensors 2021, 21, 5304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Graffy, P.M.; Sandfort, V.; Summers, R.M.; Pickhardt, P.J. Automated Liver Fat Quantification at Nonenhanced Abdominal CTfor Population-Based Steatosis Assessment. Radiology 2019, 293, 334–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sethunath, D.; Morusu, S.; Tuceryan, M.; Cummings, O.W.; Zhang, H.; Yin, X.-M.; Vanderbeck, S.; Chalasani, N.; Gawrieh, S. Automated Assessment of Steatosis in Murine Fatty Liver. PLoS ONE 2018, 13, e0197242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramot, Y.; Zandani, G.; Madar, Z.; Deshmukh, S.; Nyska, A. Utilization of a Deep Learning Algorithm for Microscope-Based Fatty Vacuole Quantification in a Fatty Liver Model in Mice. Toxicol. Pathol. 2020, 48, 702–707. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vanderbeck, S.; Bockhorst, J.; Komorowski, R.; Kleiner, D.E.; Gawrieh, S. Automatic Classification of White Regions in Liver Biopsies by Supervised Machine Learning. Hum. Pathol. 2014, 45, 785–792. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forlano, R.; Mullish, B.H.; Giannakeas, N.; Maurice, J.B.; Angkathunyakul, N.; Lloyd, J.; Tzallas, A.T.; Tsipouras, M.; Yee, M.; Thursz, M.R.; et al. High-Throughput, Machine Learning-Based Quantification of Steatosis, Inflammation, Ballooning, and Fibrosis in Biopsies From Patients with Nonalcoholic Fatty Liver Disease. Clin. Gastroenterol. Hepatol. 2020, 18, 2081. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heinemann, F.; Birk, G.; Stierstorfer, B. Deep Learning Enables Pathologist-Like Scoring of NASH Models. Sci. Rep. 2019, 9, 18454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chaulagain, R.P.; Dinislam, K.; Shrestha, Y.; Yadav, D.K.; Ali, A. Advancing Diagnosis of Liver Cirrhosis: Why Non-invasive Methods Are the Future? Cureus 2025, 17, e99071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, A.; Connell, M.; Khetarpal, S. Digital Image Analysis of Ultrasound Images Using Machine Learning to Diagnose Pediatric Nonalcoholic Fatty Liver Disease. Clin. Imaging 2021, 77, 62–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Y.; Huang, D.Q.; Zhang, P.; Wang, M.; Wu, Y.; Nur, E.; Li, L.; Wang, H. Plasma inflammatory proteome profiles identify MASLD among children with overweight or obesity. Cardiovasc Diabetol. 2025, 24, 450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Liu, R.; An, Y.; He, F. Markers of body fat, the mediating role of alanine aminotransferase, and their association with the risk of metabolic dysfunction-associated steatotic liver disease. Eur. J. Pediatr. 2025, 184, 524. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhan, S.; Wang, X.; Wang, C.; Zhu, B.; Gao, J.; Peng, Z.; Wang, R.; Yang, Y.; Zhang, L.; Wang, T.; et al. Tryptophan derivatives as non-invasive diagnostic indicators for obesity-related MASLD in children and adolescents. Diabetes Obes. Metab. 2025, 27, 7544–7560. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zöggeler, T.; Kavallar, A.M.; Pollio, A.R.; Aldrian, D.; Decristoforo, C.; Scholl-Bürgi, S.; Müller, T.; Vogel, G.F. Meta-analysis of shotgun sequencing of gut microbiota in obese children with MASLD or MASH. Gut Microbes 2025, 17, 2508951. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, D.; Leitman, M.; Pawar, S.; Shera, S.; Hernandez, L.; Jacobs, J.P.; Dong, T.S. The Association Between Prevotella covers and Advanced Fibrosis in the Progression of Metabolic Dysfunction-Associated Steatotic Liver Disease. Nutrients 2025, 17, 2145. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nychas, E.; Marfil-Sánchez, A.; Chen, X.; Mirhakkak, M.; Li, H.; Jia, W.; Xu, A.; Nielsen, H.B.; Nieuwdorp, M.; Loomba, R.; et al. Discovery of robust and highly specific microbiome signatures of non-alcoholic fatty liver disease. Microbiome 2025, 13, 10. [Google Scholar] [CrossRef] [Scilit] [PubMed]


Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Amitrano, M.; Mondillo, G.; Emiliano, M.; Santoro, U.P. Applying Artificial Intelligence to Childhood Obesity: T2DM and MASLD Risk Predictive Models. Diagnostics 2026, 16, 2533. https://doi.org/10.3390/diagnostics16162533
Amitrano M, Mondillo G, Emiliano M, Santoro UP. Applying Artificial Intelligence to Childhood Obesity: T2DM and MASLD Risk Predictive Models. Diagnostics. 2026; 16(16):2533. https://doi.org/10.3390/diagnostics16162533
Chicago/Turabian StyleAmitrano, Marianna, Gianluca Mondillo, Mario Emiliano, and Umberto Paolo Santoro. 2026. "Applying Artificial Intelligence to Childhood Obesity: T2DM and MASLD Risk Predictive Models" Diagnostics 16, no. 16: 2533. https://doi.org/10.3390/diagnostics16162533
APA StyleAmitrano, M., Mondillo, G., Emiliano, M., & Santoro, U. P. (2026). Applying Artificial Intelligence to Childhood Obesity: T2DM and MASLD Risk Predictive Models. Diagnostics, 16(16), 2533. https://doi.org/10.3390/diagnostics16162533