


Abstract
Purpose: Knowledge of the length of the colon is relevant to understanding physiological and pathological function. It also has implications for diagnostic and clinical interventions, as well as for the design of delayed-release drug formulations and drug disposition modeling. Methods: Over the years, a range of different experimental methods have been employed to assess colon length. These methods vary from direct measurements on cadavers and during intraoperative procedures to measurements obtained from endoscopic and medical imaging techniques. However, no systematic review or meta-analysis of these findings has yet been carried out. In this systematic review, we identified 31 published experimental studies that measured the length of the human colon and/or its segments. Results: We synthesized the available data, comprising colon length measurements from 5741 adults and 337 children and young people, in a meta-analysis. The data contribute to our understanding of colon morphology and may have implications for clinical practice, particularly for colonoscopy and preoperative planning of surgical resections. Additionally, this review provides potential insights into anatomical correlates of functional diseases, such as constipation. Conclusions: This review highlights that non-invasive, non-destructive diagnostic imaging techniques, such as magnetic resonance imaging (MRI), can provide more physiologically relevant measurements of colon length. However, there is a need for more standardized measurement protocols and for additional pediatric data.
1. Introduction
The colon is one of the main organs of the human gastrointestinal tract, performing crucial functions such as the absorption of water and electrolytes, transport of chyme, and the formation and elimination of feces. The colon begins at the cecum, where the small intestine meets the large intestine, and ends at the rectum. The ascending colon travels upward on the right side and ends at the hepatic flexure. The transverse colon crosses the abdomen from right to left and ends at the splenic flexure. The descending colon then travels from the splenic flexure downward on the left side and transitions into the sigmoid colon at the level of the pelvic brim, which curves into the pelvic region before connecting to the rectum [1]. The clinical outcomes of procedures such as colonoscopy and surgery can be affected by variability in colon anatomy and dimensions [2,3]. Knowledge of colon length can help when planning surgical procedures and in understanding conditions like constipation. For example, colonic elongation has been related to slow transit constipation and functional fecal retention [4,5]. The length of the colon has also been correlated with the presence of diverticula [6]. Colon length measurements are also needed to interpret high-end colon motility measurements [7] and to inform the design of delayed-release drug dosage forms and drug disposition modeling.
Despite the importance of this organ, knowledge of its morphology and particularly of its length is still incomplete. Over the years, a range of different experimental methods have been employed to assess colon length. These vary from measurements on cadavers and during intraoperative procedures to endoscopic and medical imaging techniques, but no systematic review of these findings has yet been carried out.
Therefore, this review and meta-analysis aimed to systematically identify, evaluate, and synthesize studies that measured the length of the colon and/or its distinct anatomical segments using experimental methodologies.
2. Materials Methods
This review followed the guidelines outlined in the Preferred Reporting Items for Systematic Reviews and Meta-analysis of Diagnostic Test Accuracy Studies (PRISMA-DTA) statement [8]. The protocol was developed in advance of conducting the work and it was registered with the International Prospective Register of Systematic Reviews (PROSPERO, registration number CRD42023465879).
2.1. Search Strategy
A comprehensive electronic search was carried out across three databases: Web of Science, MEDLINE (Ovid), and EMBASE (Ovid). Date restrictions were not applied. The initial search was conducted in September 2023, and it was last updated in May 2024. Advanced literature search techniques were employed using “AND” and “OR” operators to refine or broaden the search scope. Boolean search strategies were utilized to locate primary sources, and relevant journal paper references were examined. The search terms were expanded beyond colon length, incorporating synonyms and varying search words such as (colon anatomy or colon morphology) to explore a broader spectrum of hits. Reference chaining and manual searches on alternative engines such as Google and Google Scholar were carried out to identify potential hits not found in the primary databases. All references retrieved from electronic databases were imported into EndNote reference management software version 20.5 (Clarivate, London, UK).
The search strategy and keywords used in the MEDLINE and Embase (OVID) database were as follows:
- 1—((colon or colorect* or colonic*) adj1 (length* or measur* or size* or anatomy*)).ti,ab.
- 2—(“large intestine” adj1 (length* or measur* or size* or anatomy*)).ti,ab.
- 3—(“large bowel” adj1 (length* or measur* or size* or anatomy*)).ti,ab.
- 4—(rat or rats or mouse or mice or swine or porcine or murine or sheep or lambs or pigs or piglets or rabbit or rabbits or cat or cats or dog or dogs or cattle or bovine or monkeys or trout or marmoset $1).ti. and animal experiment/.
- 5—animal experiment/ not (human experiment/ or human/).
- 6—4 or 5.
- 7—1 or 2 or 3
- 8—7 not 6.
2.2. Eligibility Criteria
Selection of studies was carried out following predefined criteria.
Eligible studies for the review included randomized controlled trials, cross-sectional studies, case–control studies, cohort (longitudinal) studies, observational studies (of all types), cohort studies, and non-randomized controlled trials that measured the length of the colon and/or its distinct anatomical segments using various experimental methodologies. All methodologies were eligible, including computed tomography (CT), magnetic resonance imaging (MRI), X-ray radiography, surgical approaches, and cadaveric investigations. Only studies involving human participants (including adults, children, males, and females, healthy and patients) were considered for inclusion. The primary outcome of interest was colon length, either the total length of the colon and/or the lengths of specific anatomical segments (namely, the cecum colon, ascending colon, transverse colon, descending colon, sigmoid colon, and rectum). The review also aimed to appraise the various techniques and tools used to measure colon length.
Exclusion criteria were studies not published in English language, case reports, review articles (including meta-analyses), editorials, replies, opinion pieces, conference abstracts, meeting abstracts, books, or book chapters. All non-human studies were excluded as well.
2.3. Study Selection and Data Extraction
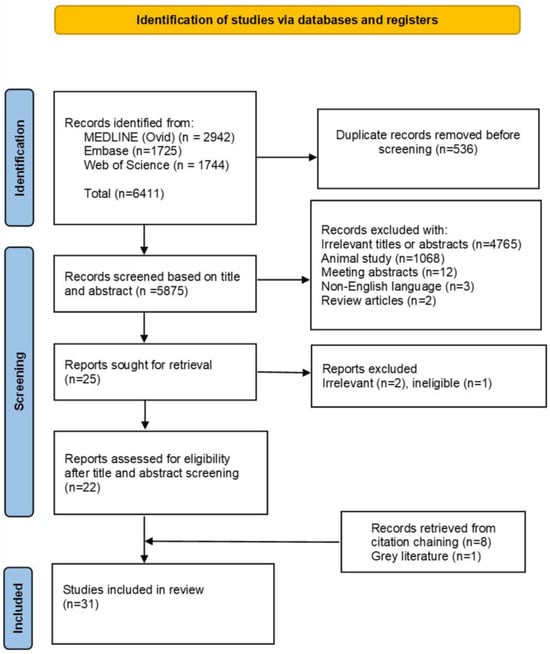
All references retrieved from the three databases underwent a systematic review process. Firstly, two reviewers (F.A. and T.A.) removed duplicate papers across the databases. They then independently screened and filtered titles and abstracts based on the above inclusion and exclusion criteria. Full manuscripts of the identified studies were then sourced. They then assessed the eligibility of the studies on the full manuscripts, providing justifications for their inclusion and exclusion decisions. For any disagreement, the initial two reviewers discussed the matter based on the criteria and if agreement could not be reached, the discussion was escalated for moderation by a third reviewer (L.M.) until consensus was reached. A PRISMA flowchart was constructed to capture the selection process of both included and excluded studies (Figure 1).
Figure 1.
PRISMA flow diagram for systematic reviews showing the process used to identify the papers included in the systematic review.
Following this, two reviewers (F.A. and H.F.) carried out data extraction from the included papers and designed a summary table containing author details, publication date, location, study type, population characteristics, age distribution, sex ratio, presence or absence of a comparison group, and colon assessment techniques. An additional reviewer (L.M.) was enlisted to assist with data extraction and to moderate cases of disagreement through discussion.
2.4. Quality Assessment of Included Studies
Quality and bias assessments of the included studies were conducted by the same two reviewers (F.A. and H.F.) using the Newcastle–Ottawa Quality Assessment Scale (NOS), adjusted for cross-sectional studies [9]. The scale comprises three categories: selection, comparability, and outcome, with a maximum total score of 10 points for all categories. Selection criteria include representativeness, sample size, nonexposed cohort, and measurement tool, with a maximum score of 5 points. Comparability assesses the measurement of confounding factors, with a maximum score of 2 points. Outcome evaluates outcome assessment and statistical tests, with a maximum score of 3 points. Each category has different scoring scales. Reviewers assign scores based on these criteria, with higher scores indicating higher research methodology quality.
The NOS criteria were modified based on the review requirements [9]. The bias assessment criteria included participant selection (type, age, sex), a sample size of more than twenty participants, clear descriptions of measurement tools and techniques, comparability, type of assessment, and statistical tests used, providing a comprehensive framework for bias assessment in the analyzed cross-sectional studies. Quality and risk of bias for the studies included in the review were independently evaluated by two reviewers (F.A. and H.F.). These studies varied in study type, with the majority being retrospective. Assessment scoring ranged from 0 to 10 points, with 0–4 points considered low quality, 5–6 satisfactory, 7–8 good, and 9–10 high quality.
2.5. Meta-Analysis Methods
All mean values of the length of the colon and/or of its segments were extracted from the papers reviewed in order to combine them and determine overall mean values and variability. The pediatric values varied considerably with age; hence, the meta-analysis was split into two parts. All the adult colon and colon segment lengths were grouped together. Secondly, the pediatric total colon length values were plotted against age; there were only a few data available for individual colon segment lengths and therefore these were not pooled into an overall analysis.
3. Results
3.1. Search Results
Twenty-two papers satisfying the inclusion/exclusion criteria were identified and included for data extraction. Eight additional papers were identified through cross-referencing plus one from the grey literature, bringing the total to thirty-one included papers. Overall, this body of work comprised colon length measurements carried out on 5741 adults and 337 children and young people. The literature search hits, identification, and screening process are summarized as a PRISMA diagram in Figure 1.
3.2. Quality Assessment of Included Studies
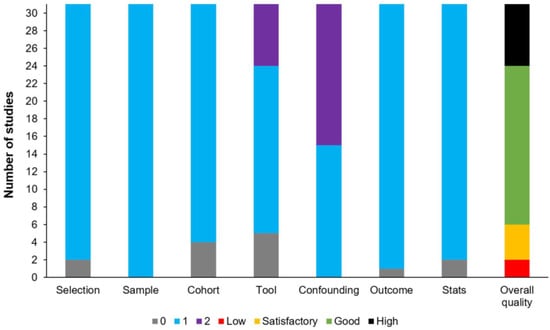
Figure 2 shows the NOS assessment result. Varying levels of bias were identified as follows: seven studies were rated as high quality, eighteen as good, four as satisfactory, and two as low, particularly in terms of selection and comparability of research groups, and determination of exposure or outcome. Common issues included non-representative samples, insufficient control for confounding variables, and high non-response rates, contributing to higher bias levels. While some studies exhibited strong methodologies and comparability, others lacked clarity.
Figure 2.
Newcastle–Ottawa Quality Assessment Scale for the studies included in the review.
3.3. Demographics of the Included Studies
Table 1 provides an overview of the demographics in the 31 studies included. These studies examined colon length using various methods and techniques, with some assessing the entire colon while others focused on specific segments. Among the included studies, eleven were conducted in the UK [2,10,11,12,13,14,15,16,17,18,19] with three of them performed by the same research group [12,13,14]. Five studies originated from the USA [20,21,22,23,24], four from Japan [25,26,27,28], two conducted by the same research group [25,28], two from India [29,30], and one each in Australia [31], Ethiopia [32], France [3], Italy [6], New Zealand [33], South Africa [34], Denmark [7], Canada [35], and Nigeria [36].
Table 1.
Overview of the included studies detailing population, demographics, and colon length measurement techniques employed.
3.4. Colon Length Assessment Methods
Table 2 presents the data on colon length extracted from each study, categorizing separately measurements carried out on total colon length and/or separate anatomical segments, which reflects the respective study designs and purposes. The studies were classified according to the techniques employed in assessing colon length. The measurement values listed in Table 2 are all expressed in centimeters.
Table 2.
Measured values of the length of anatomical colon segment and/or total colon length listed by reviewed study with the corresponding colon length measurement techniques employed. Values are expressed in cm.
3.4.1. Cadaver Assessment Studies
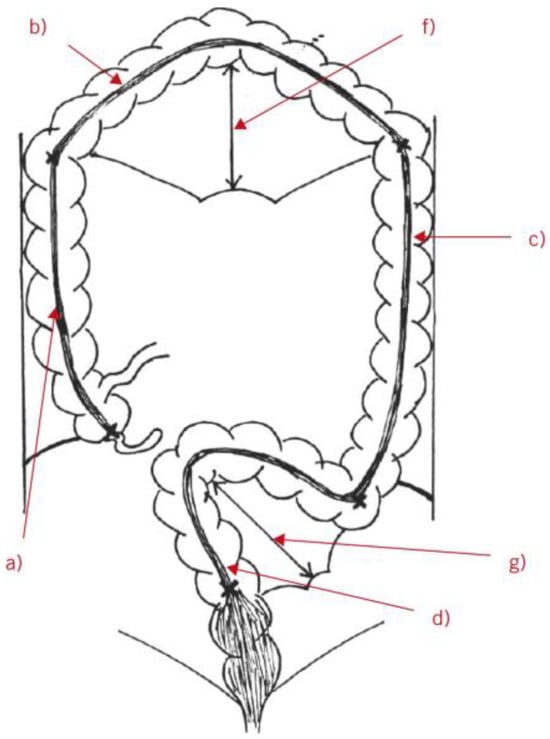
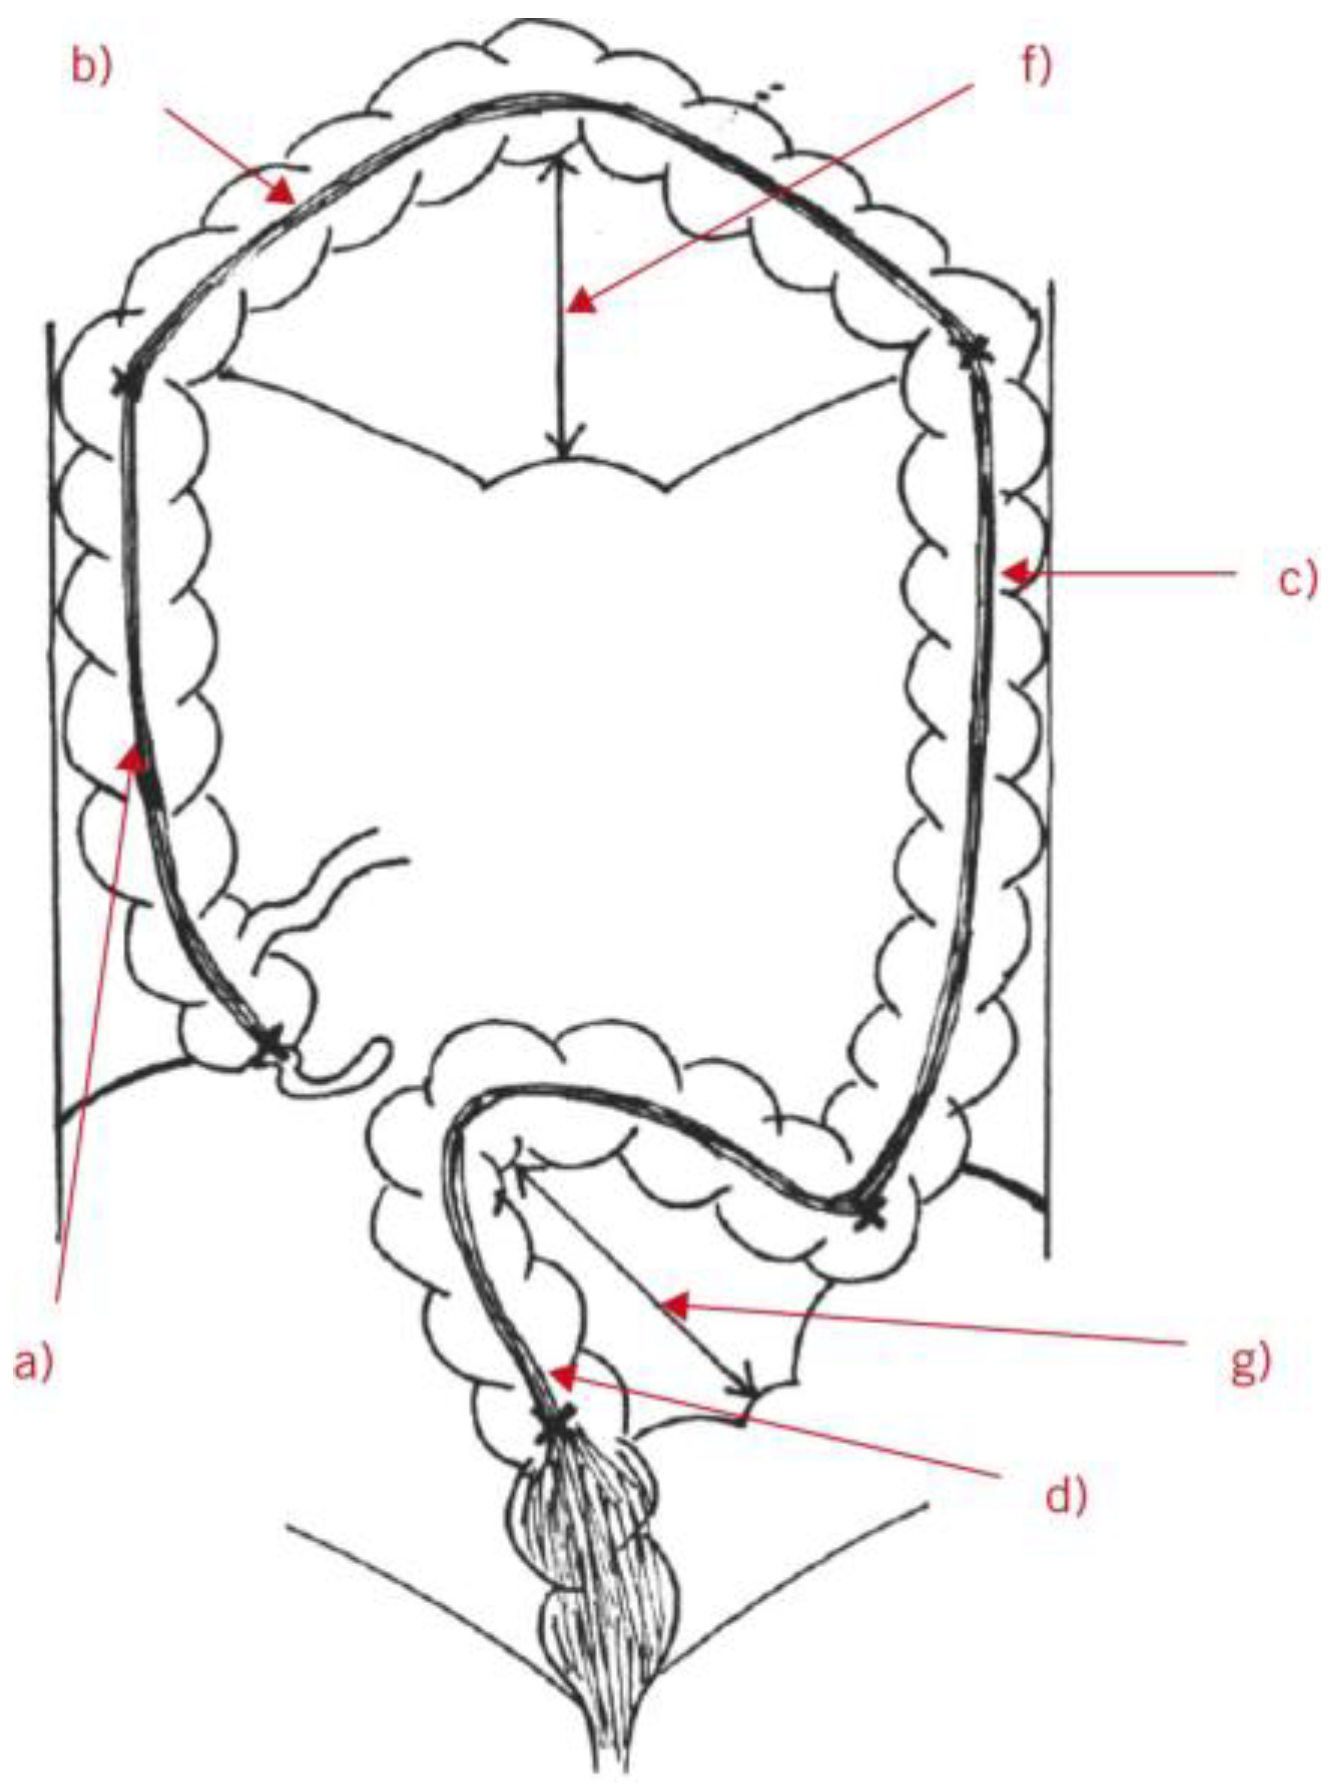
Nine studies carried out colon measurements on cadavers (Figure 3) utilizing various measurement tools, including surgical tape or a ruler [3,10,11,18,20,29,30,31,36]. Some of these studies included comparisons between cadavers and living subjects [29,31,36]. Some of these investigations evaluated both total colon length and length of segments, while others specifically focused on individual segments, such as the sigmoid colon [29,30,36]. A strong positive relationship between body weight and colon length was also suggested [3].
Figure 3.
Diagram showing the colonic length measurements performed with a flexible tape measure on human cadavers that were fixed using a mixture of formaldehyde, ethanol, and methanol. The labels indicate, respectively, the following: (a) length of ascending colon (plus cecum); (b) length of transverse colon; (c) length of descending colon; (d) length of rectosigmoid colon; (f) height of transverse mesentery; (g) height of sigmoid mesentery. Reproduced with permission from Phiilips, Annals of the Royal College of Surgeons of England [18]; published by the Royal College of Surgeons of England, 2015.
3.4.2. Intraoperative Assessment
Five studies [13,29,32,35,36] assessed colon length in patients undergoing surgical procedures such as laparotomy or for conditions like sigmoid volvulus. Measurements were carried out using tape or suture thread. Some investigations involved comparisons between living subjects and cadavers [36], while others compared patients with and without a history of sigmoid volvulus [32]. This study found that a sigmoid colon that is elongated with a long and wide mesentery, but maintains a consistent base, is strongly associated with an increased risk of sigmoid volvulus [32].
3.4.3. Colonoscopy Assessment Studies
Five studies [15,16,22,24,26] employed colonoscopy to evaluate colon length. Colonoscopy involves the insertion of a camera catheter from the ano-rectum through the colon for diagnostic purposes and can also enable colon length measurements. These studies utilized various colonoscopy techniques, incorporating aids such as computer-aided measurements or magnetic endoscopic imaging (MEI). MEI utilizes small radio transmitter coils placed along the catheter that allow three-dimensional tracking of the catheter as it moves around the colon [15,16]. Some of these investigations also conducted simultaneous comparisons with alternative techniques, such as computed tomography colonography (CTC) [22,24,26], to investigate possible differences. There was a significant difference in overall colonic length between CT colonography and conventional colonoscopy. The number of acute angle flexures and the degree of tortuosity detected with CT colonography were higher than expected [24].
3.4.4. Radiological Barium Enema Assessment Studies
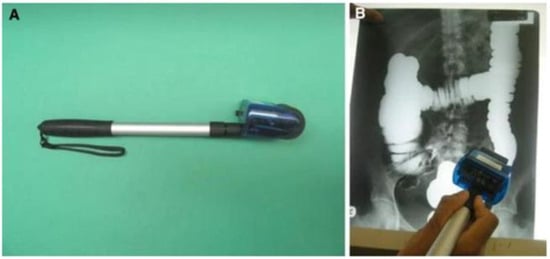
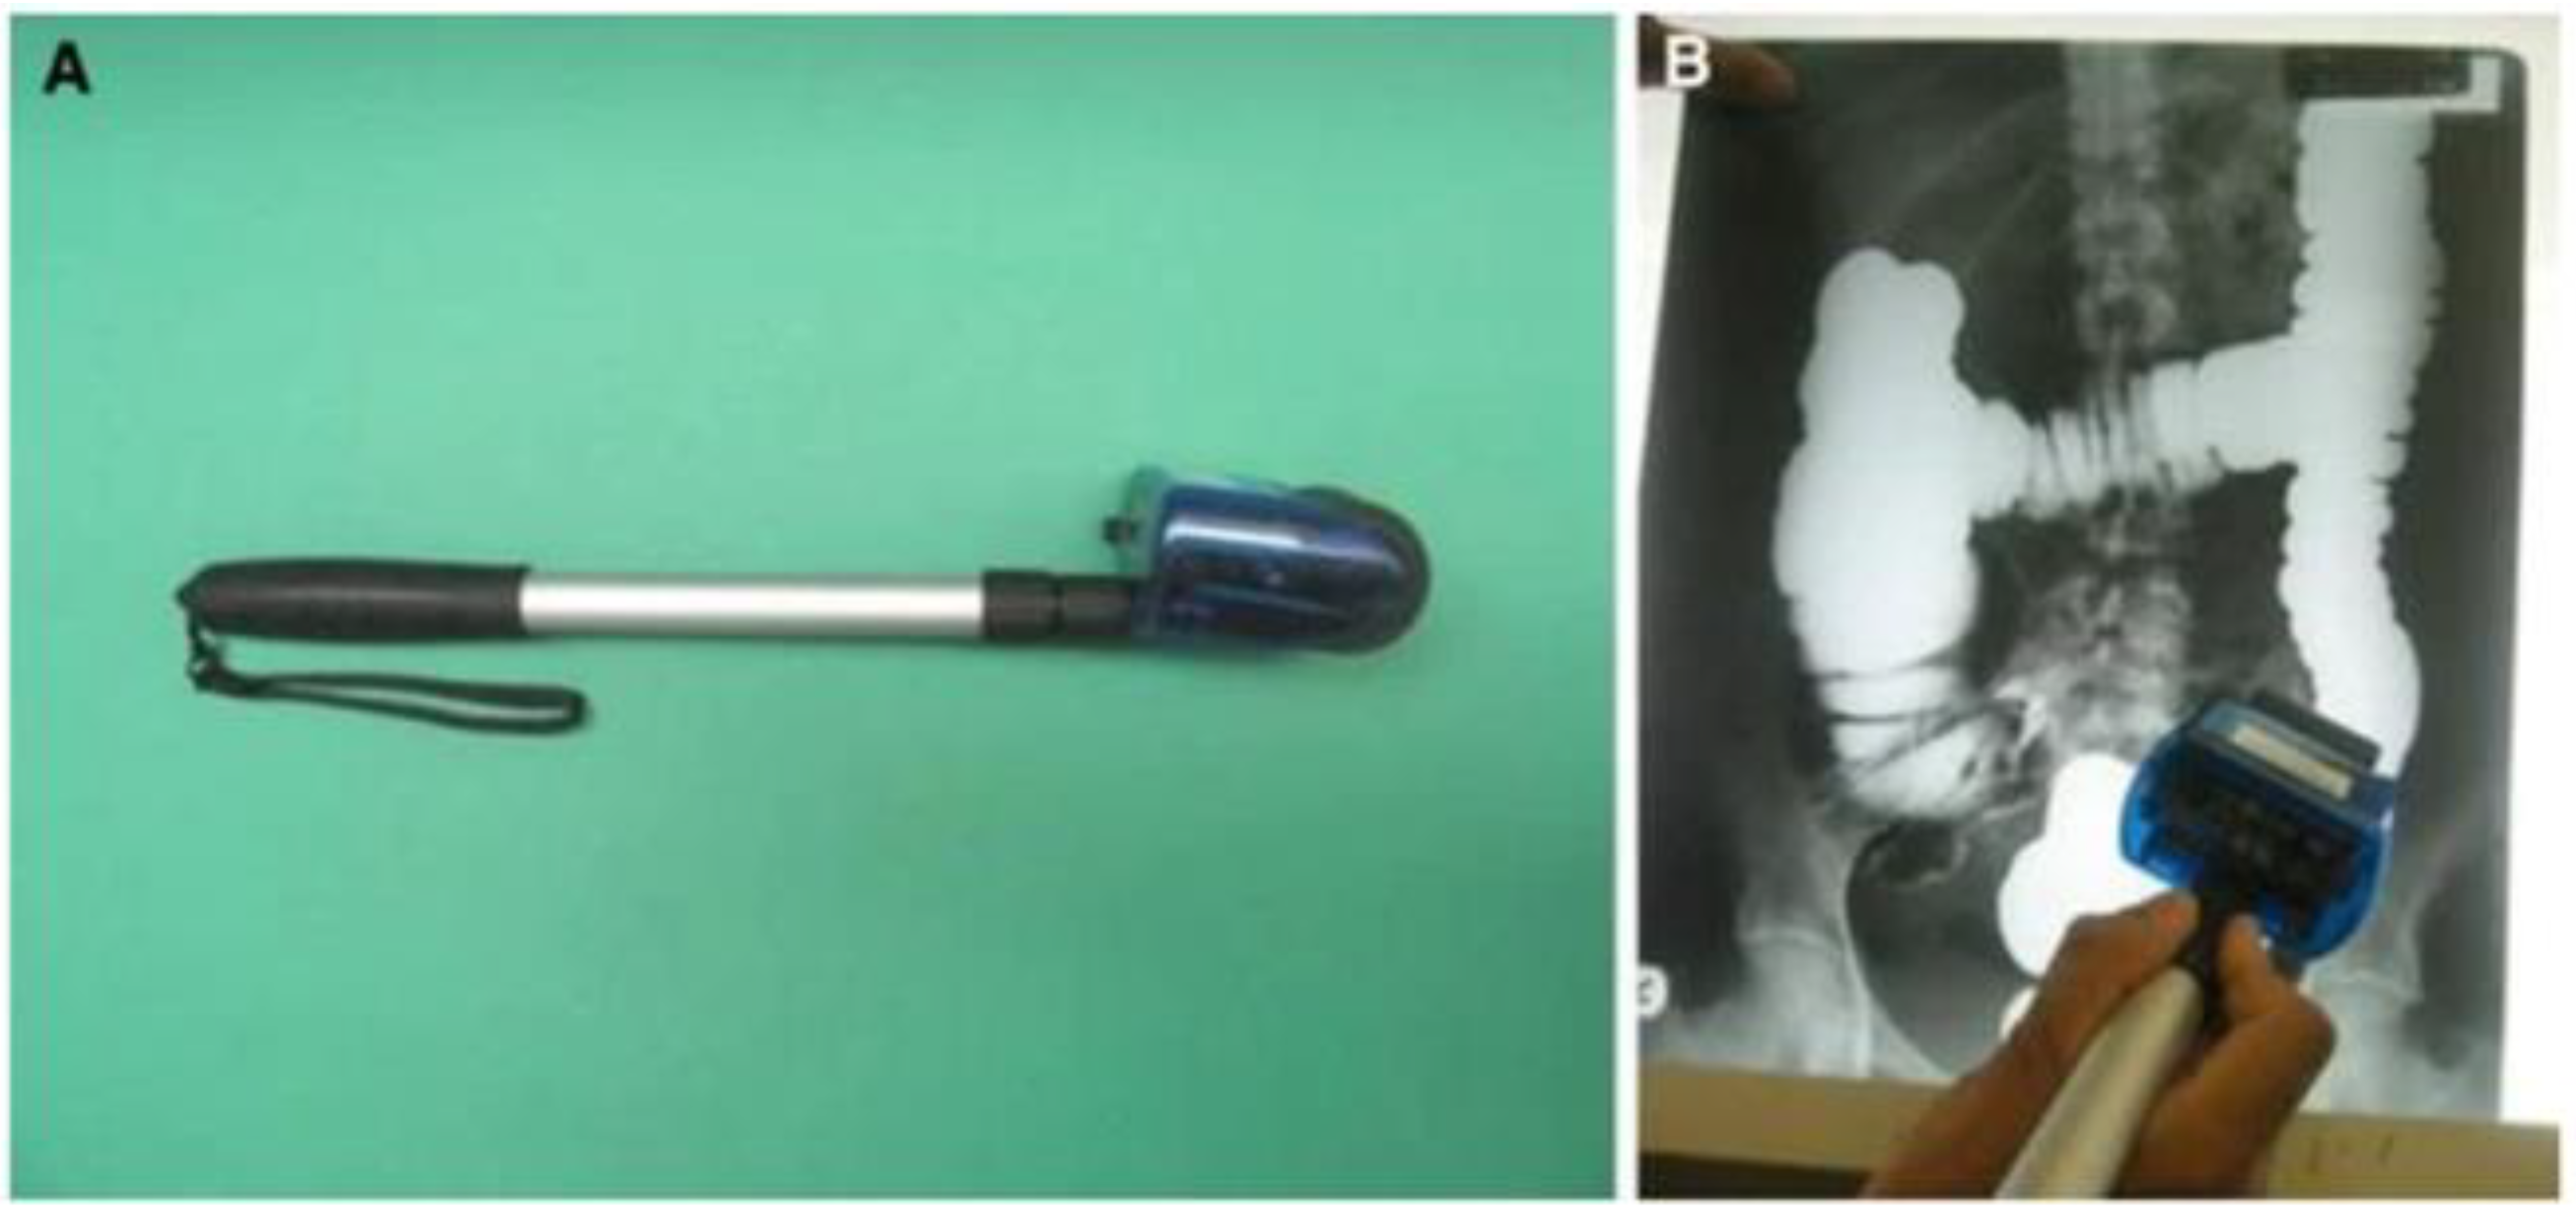
Six studies [12,14,25,28,31,34] employed the radiological barium enema technique, which exploits X-ray imaging of the colon and involves prior administration of luminal contrast mediums containing barium to provide X-ray contrast (Figure 4). Measurements are then carried out on the films using tools such as opisometer wheels, which is an instrument for measuring the lengths of arbitrary curved lines, or ruler measures to measure the colon either in its entirety and/or by segment. Some studies included comparisons of this technique with alternative methods, such as cadaveric measurements [31], while others evaluated only the effectiveness of the barium enema imaging technique itself. The comparison of barium enema with cadaver studies for colon length measurement indicated that the barium enema method was a reliable tool compared to the cadaveric measurement [31].
Figure 4.
(A) Image of an opisometer. (B) Shows an investigator using an opisometer to measure the colon. The wheel measures length as it is run along the colon in the barium enema radiograph. Panel figure reproduced with permission from Madiba, Surgical and Radiologic Anatomy [34]; published by Wiley, 2008.
3.4.5. Computed Tomography Colonography Assessment
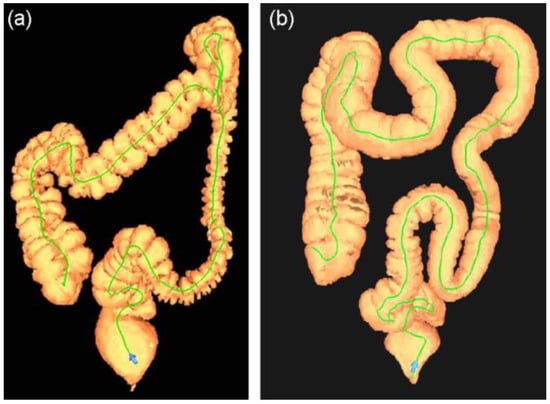
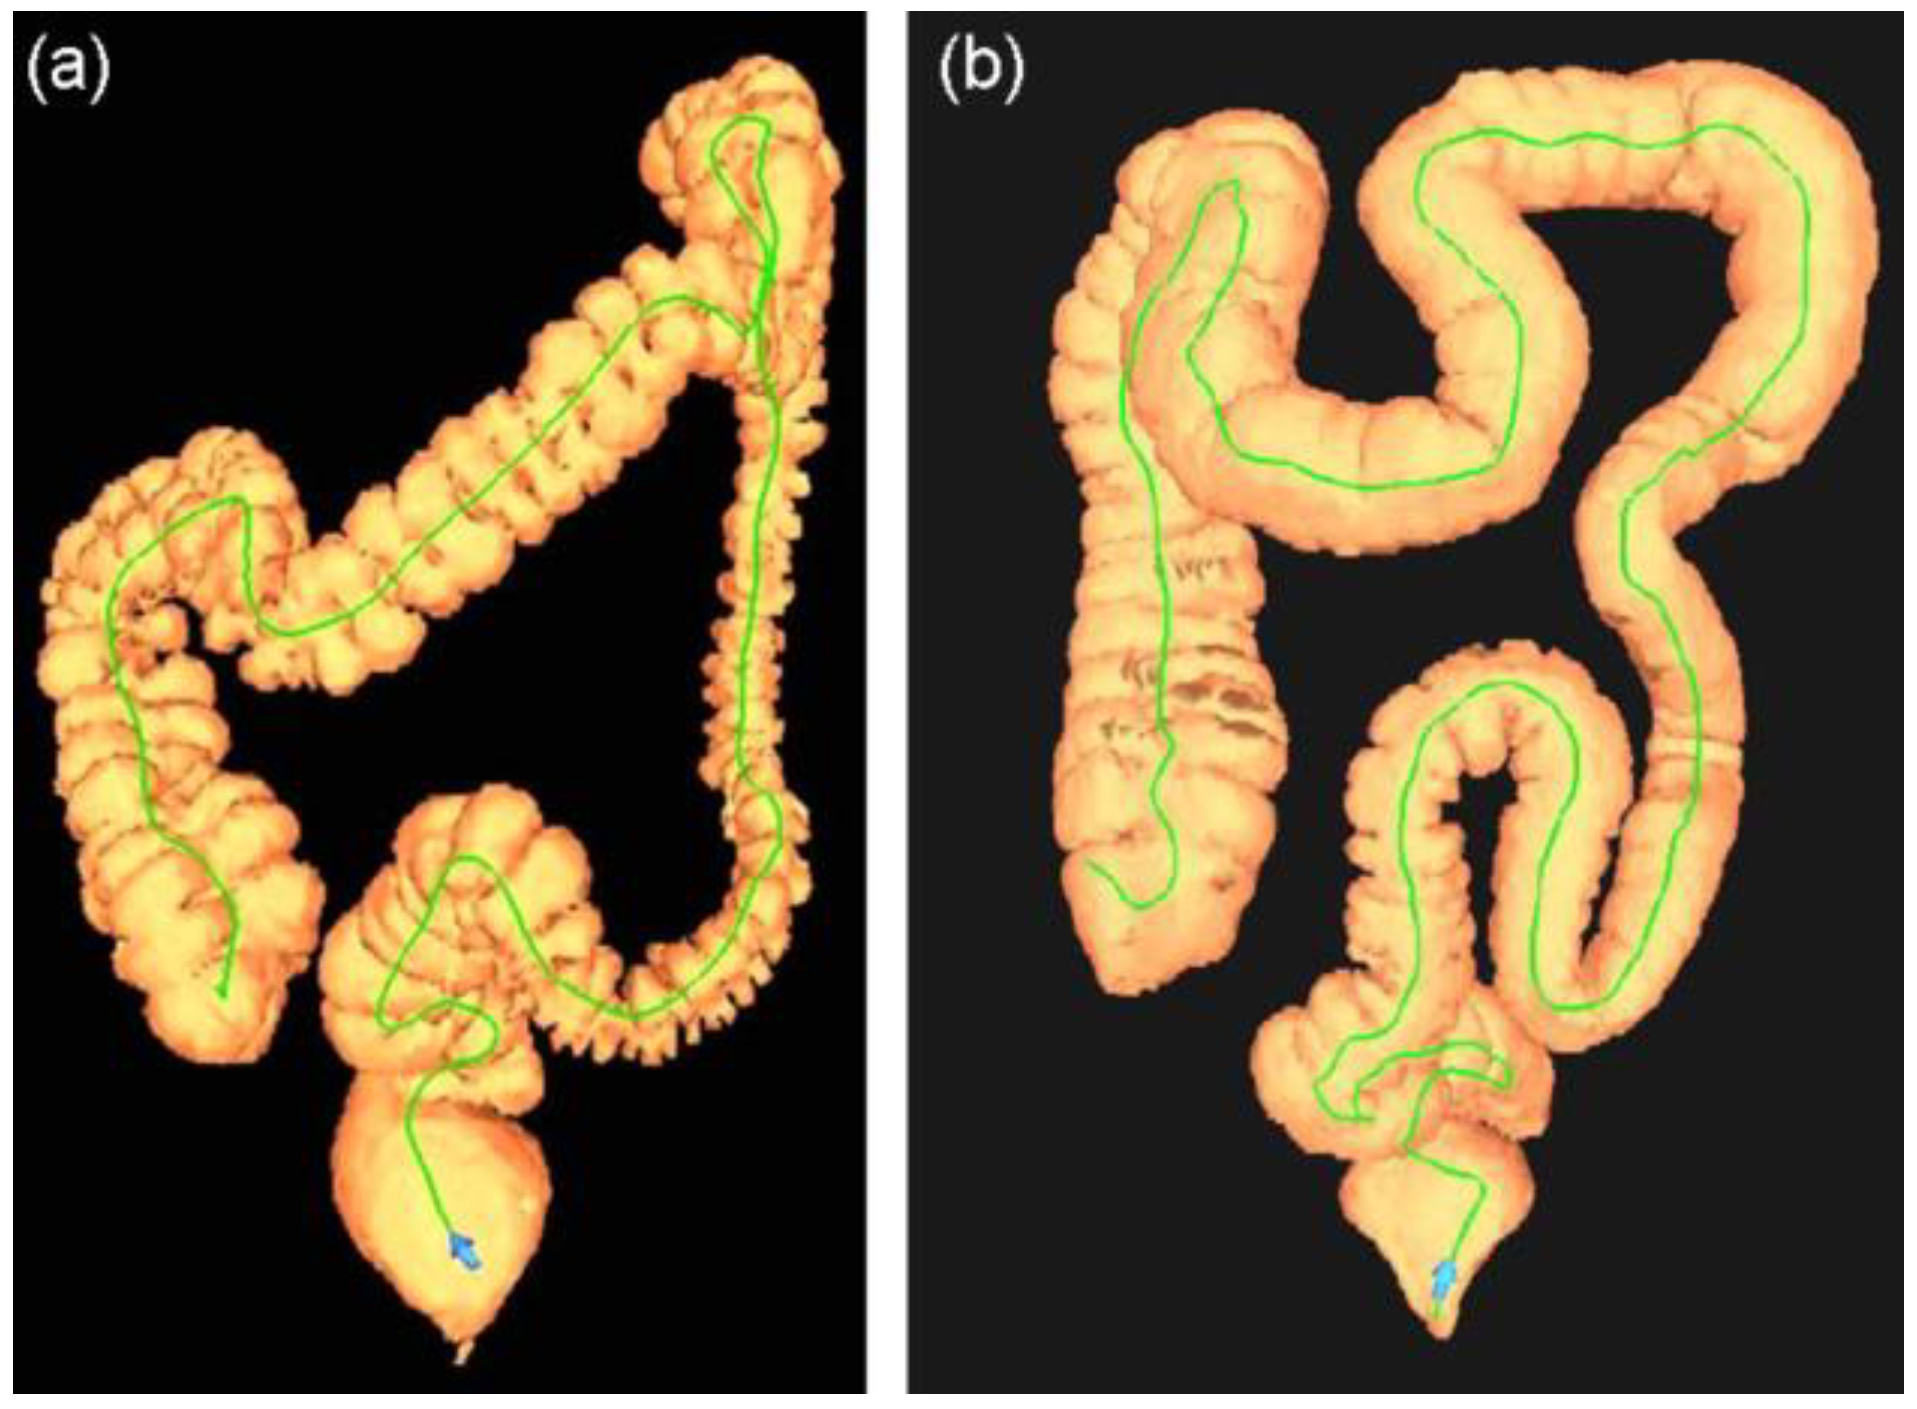
Ten studies [6,17,19,21,22,23,24,26,27,33] carried out colon length measurements using CT colonography (CTC). CT utilizes X-ray beams rotating around the patient, which allows three-dimensional imaging of the abdomen. The measurement techniques utilized across these studies are largely uniform, employing automated centerline measurements to generate a 3D map (Figure 5). Additionally, some of these investigations compared the efficacy of CTC methods with traditional colonoscopy techniques [22,24,26]. CT colonography (CTC) is a diagnostic procedure designed to detect colonic adenomatous lesions and is less invasive than colonoscopy and it allows examining colonic morphology at the same time [26].
Figure 5.
Examples of computed tomography colonography (CT) three-dimensional reconstructions of the colon. The green line shows the centerline calculated automatically for endoluminal navigation and colon length measurement. (a,b) illustrate different colon morphology and tortuosity in these two patients. Reproduced with permission from Eickhoff, Digestive and Liver Disease [24]; Wiley, 2010.
3.4.6. Magnetic Resonance Imaging and 3D-Transit Assessment
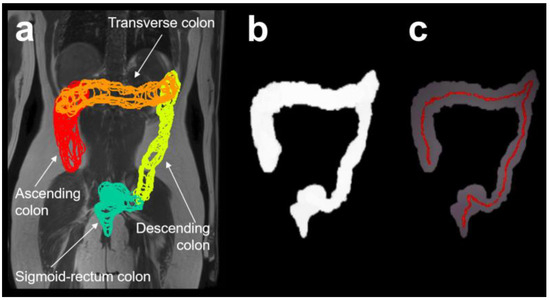
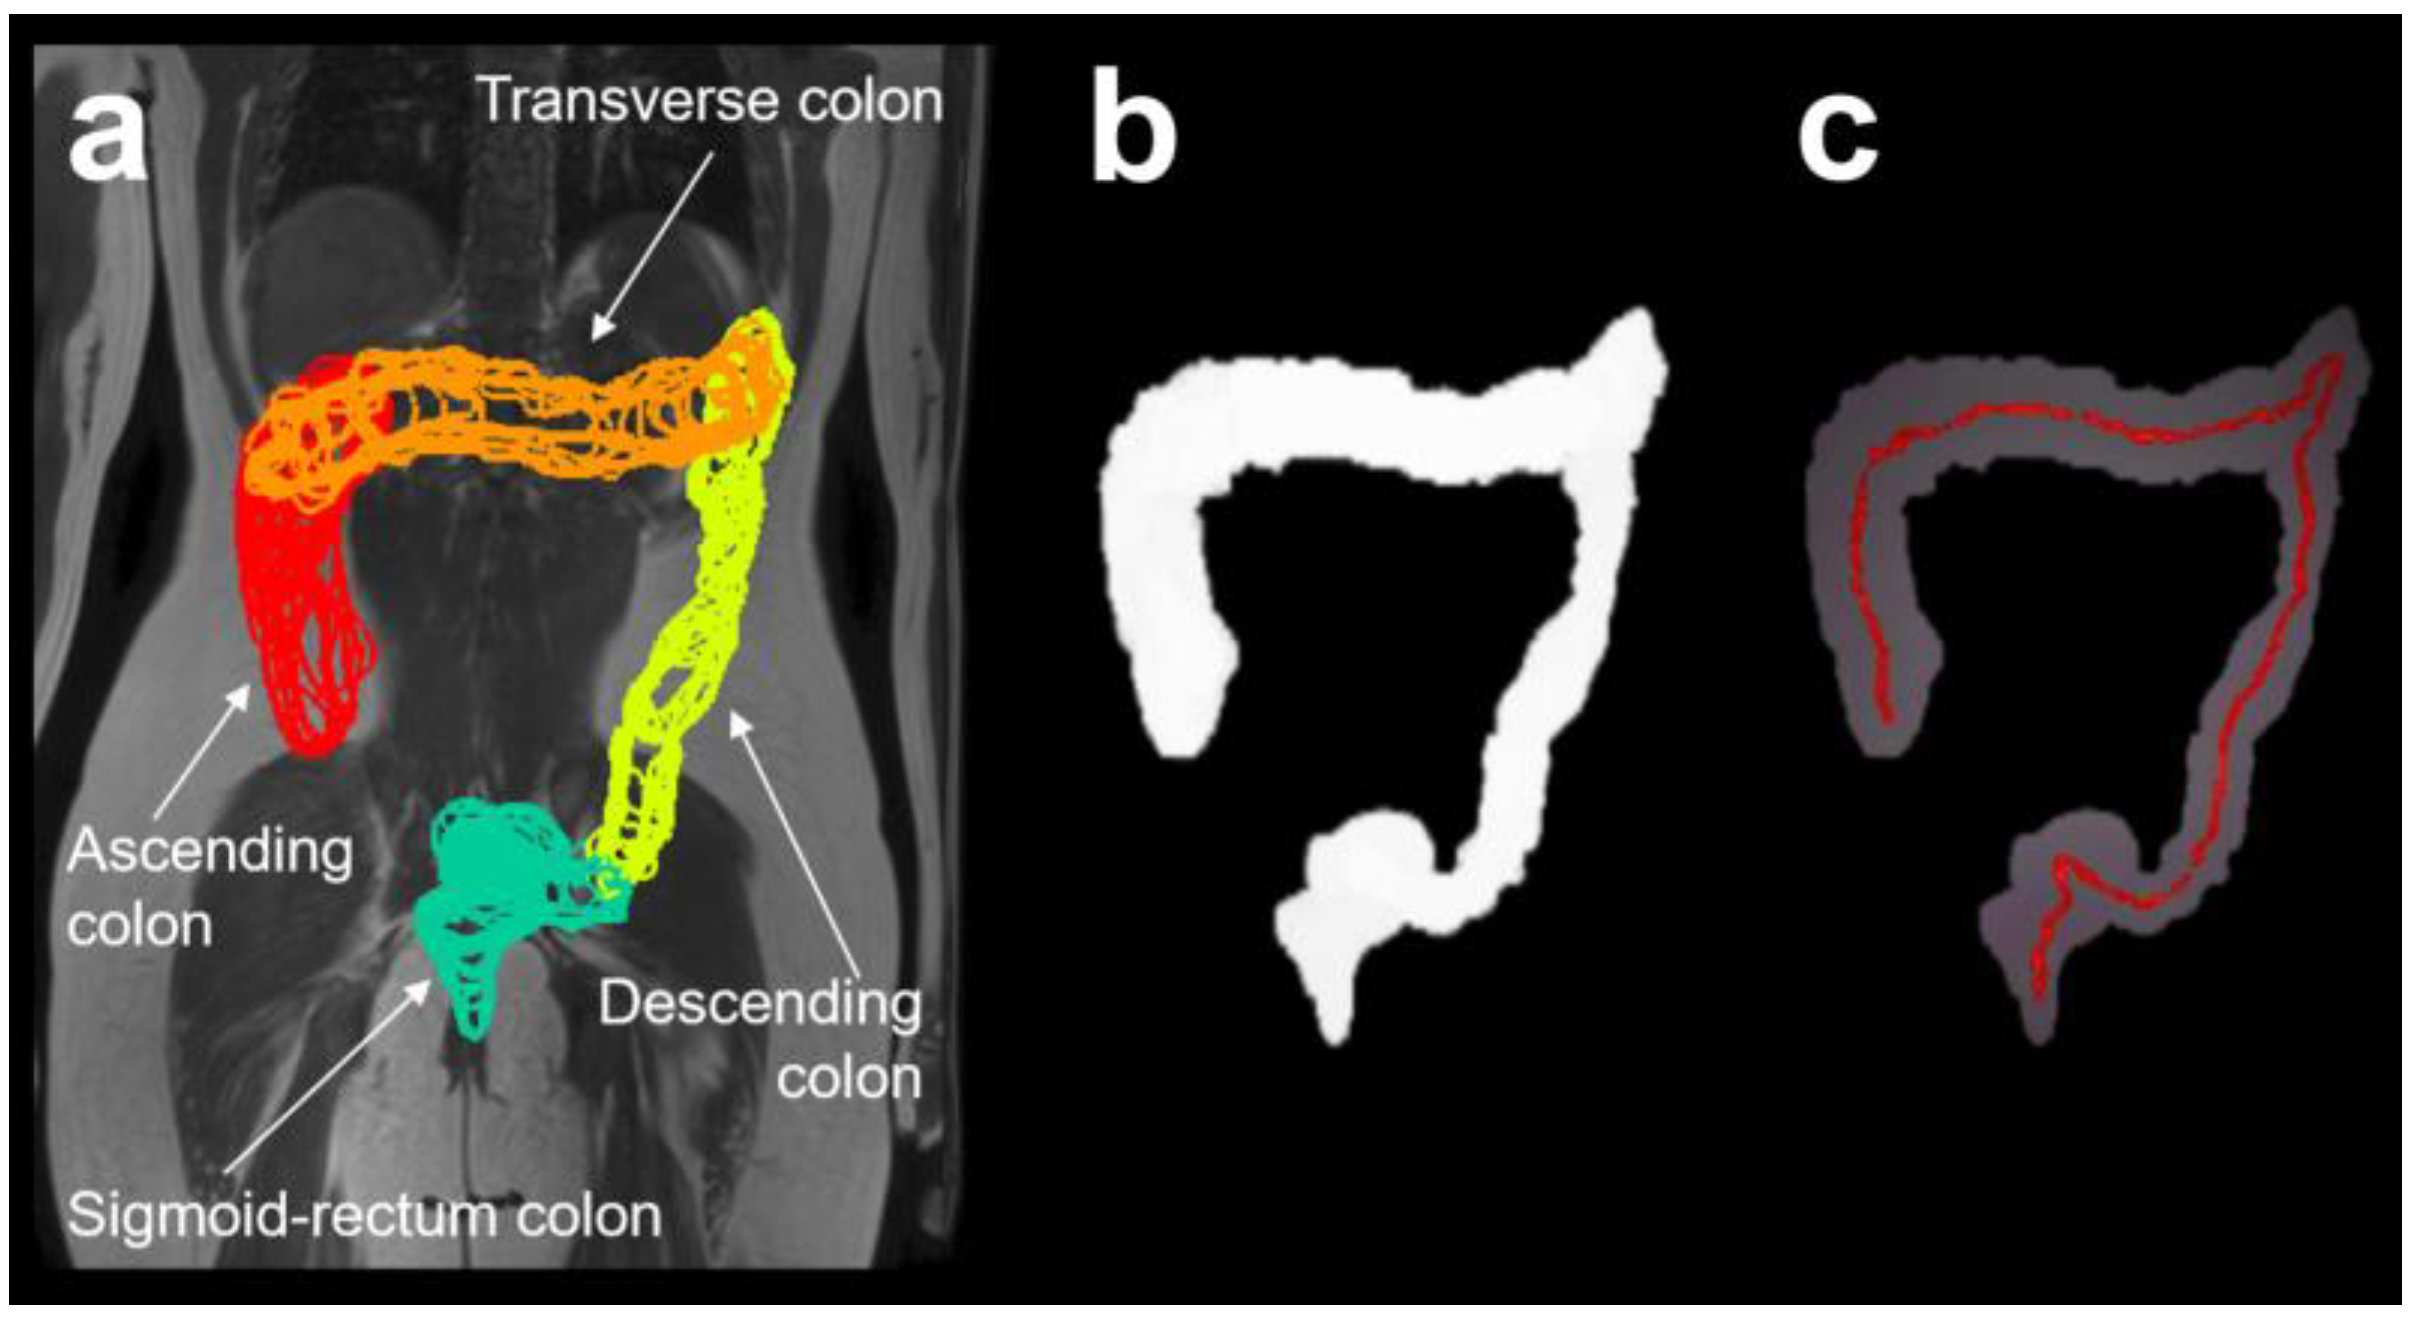
Two studies [2,7] explored colon length using MRI techniques (Figure 6). MRI uses radio waves to transmit and receive a signal from the water inside the body; the signal is localized spatially, and three-dimensional images of the abdomen can be reconstructed. One of the studies compared MRI findings with another remote tracking system called 3D-Transit, which utilizes electromagnetic tracking capsules [7]. The study showed that the 3D-Transit method reliably estimated colorectal length with a consistent level of accuracy when compared to MRI-derived measurements, showing acceptable variation. Moreover, it demonstrated reliability across recordings conducted on two consecutive days [7]. The second study utilized image processing visualization software to compare colon characteristics between healthy children and those with functional constipation [2].
Figure 6.
Example of MRI segmentation and 3D skeletonization measure of colon length. (a) A 2D representation of the regions of the colon superimposed to a coronal MRI scan of the body (ascending colon represented in red, transverse colon in orange, descending colon in yellow, and sigmoid/rectum colon in green). (b) A 2D projection of the overall binary mask for the entire colon. (c) A 2D projection of the 3D colon length path line (shown in red). Reproduced under Creative Commons Attribution License from reference [2].
3.5. Meta-Analysis
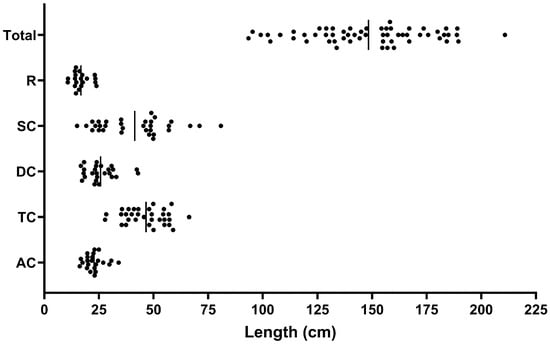
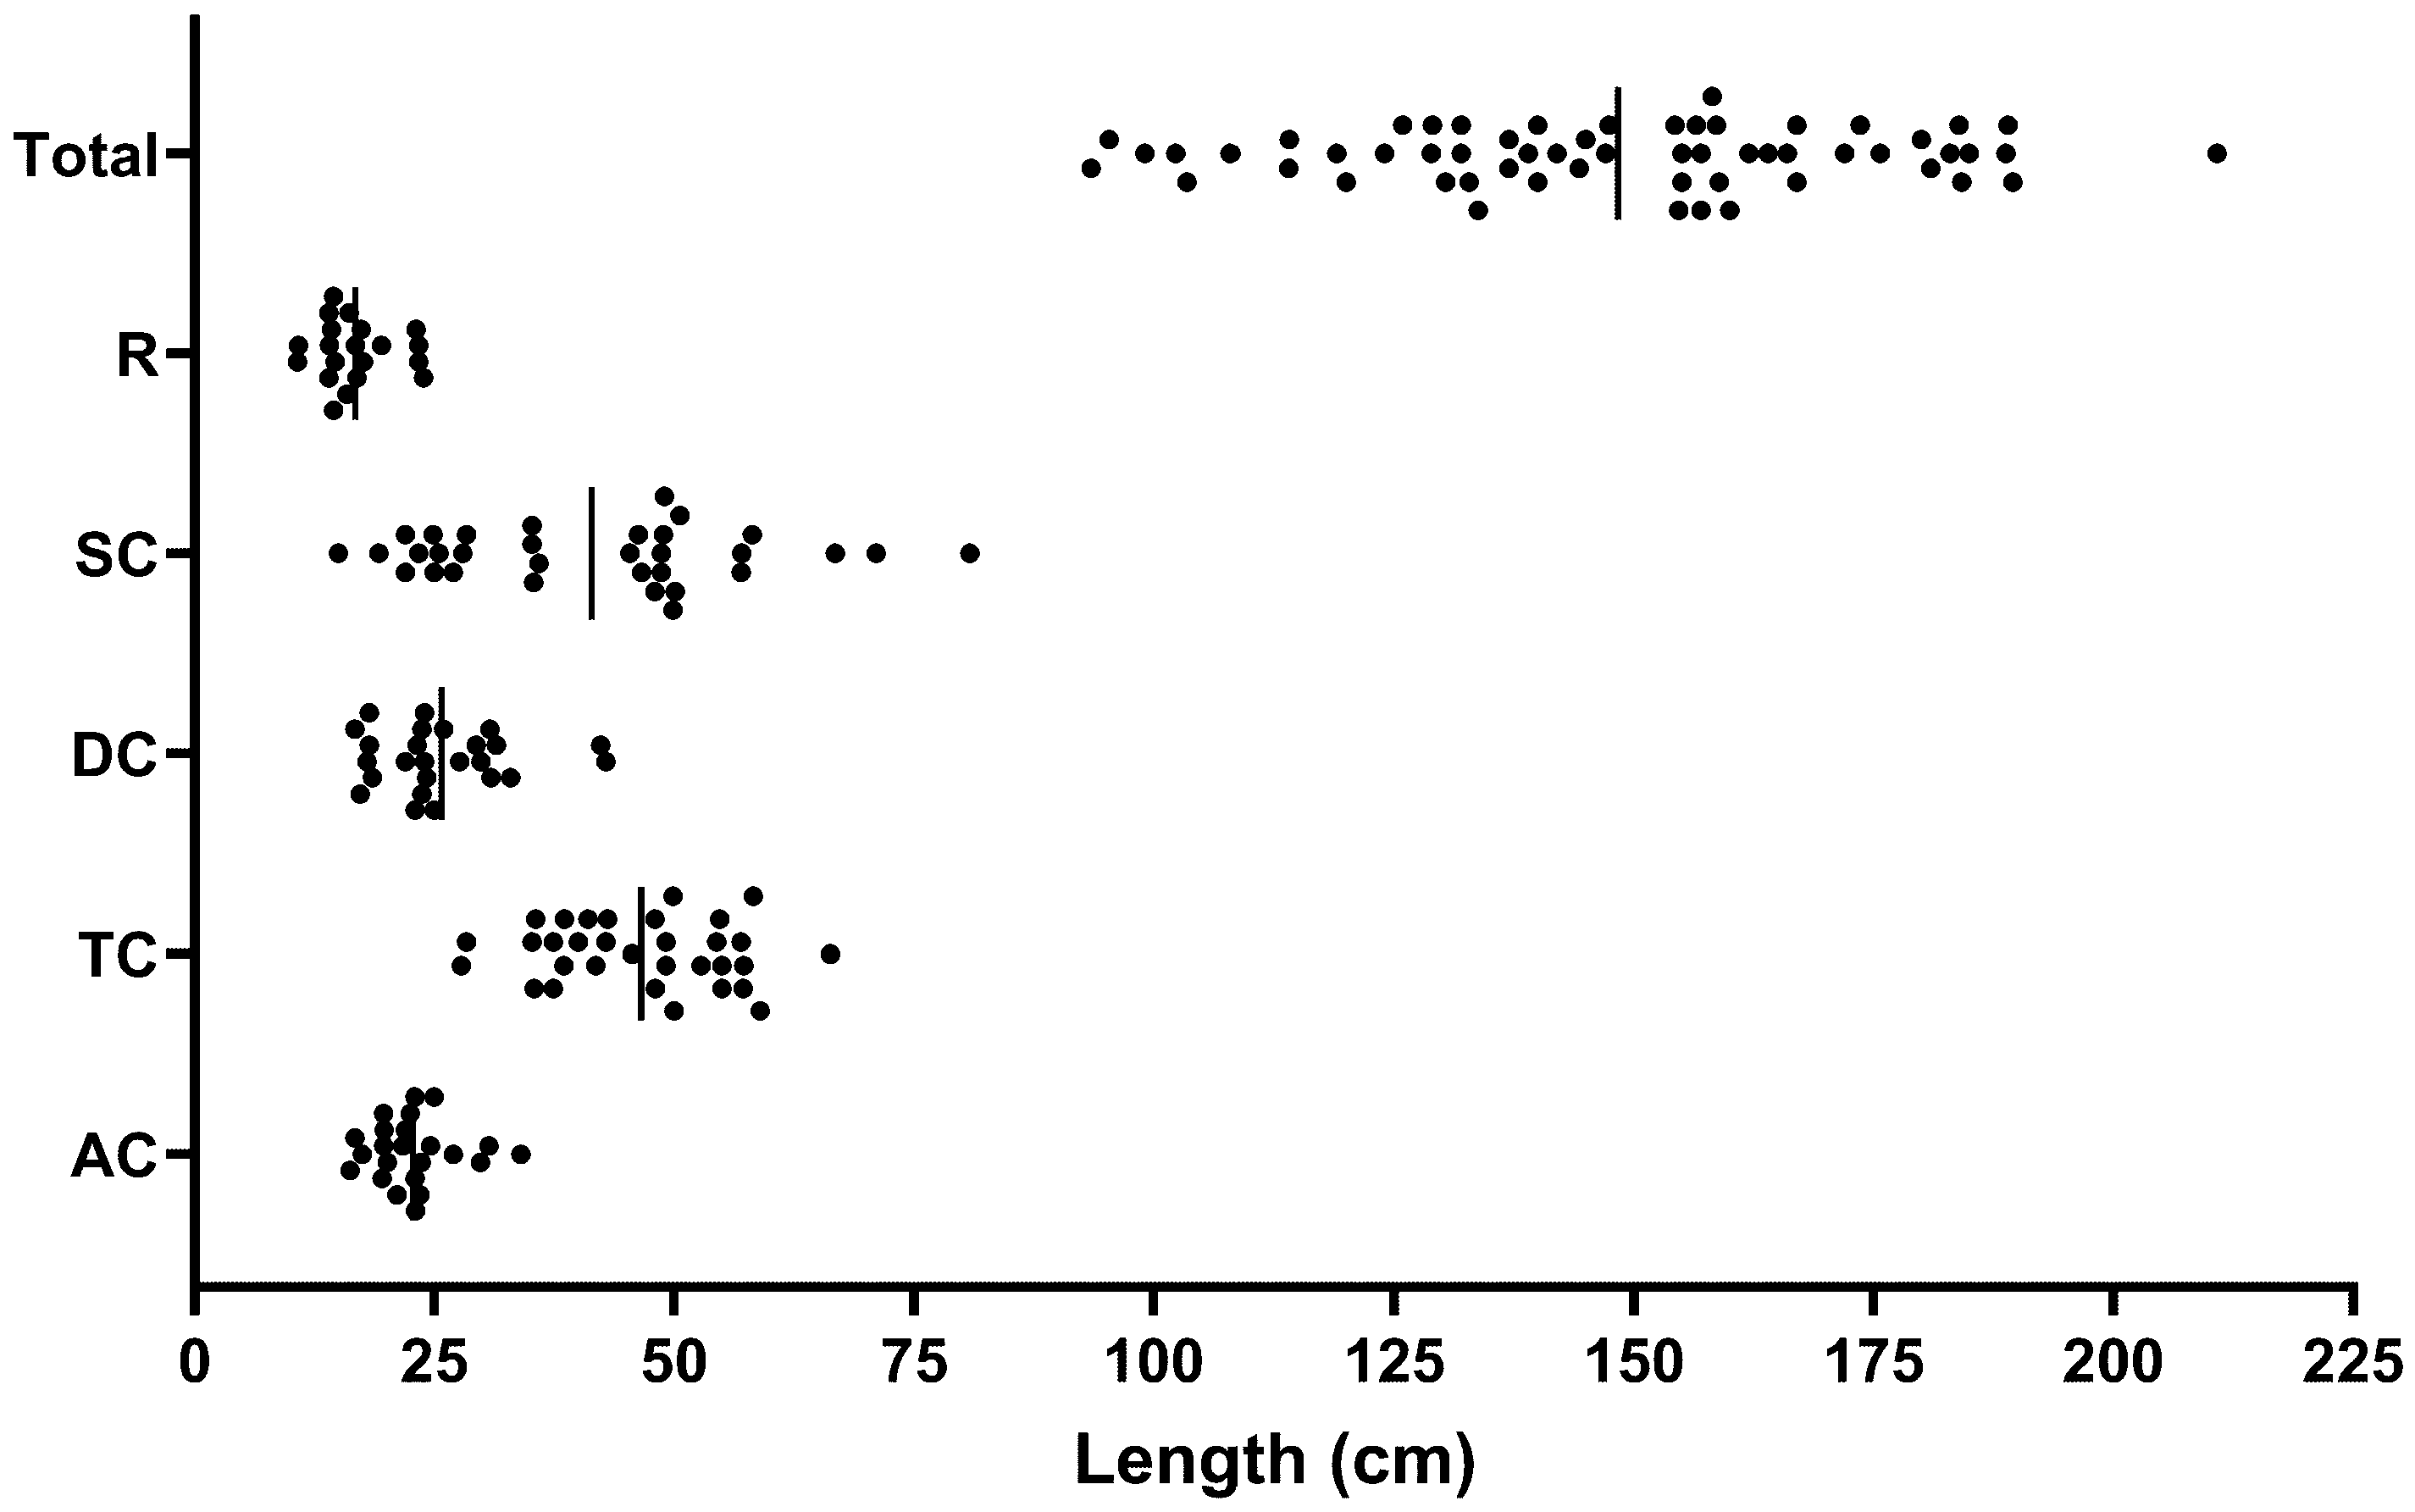
All the available mean values of the length of the adult colon and/or its anatomical segments, for all techniques, are plotted in Figure 7 and the descriptive numerical values are reported in Table 3. The data show the variability in the values reported, which have coefficients of variation between 19% and 39%, with the sigmoid colon being the most variable length. Meta-analysis of the data showed that the overall mean of the mean lengths of the adult colon was 148.3 cm with a standard deviation of 27.1 cm.
Figure 7.
Mean values of the adult length of the colon and/or of its anatomical segments extracted from the reviewed literature. The solid vertical lines represent the overall mean value.
Table 3.
Descriptive summary values of the length of the colon and/or of its anatomical segments extracted from the reviewed literature.
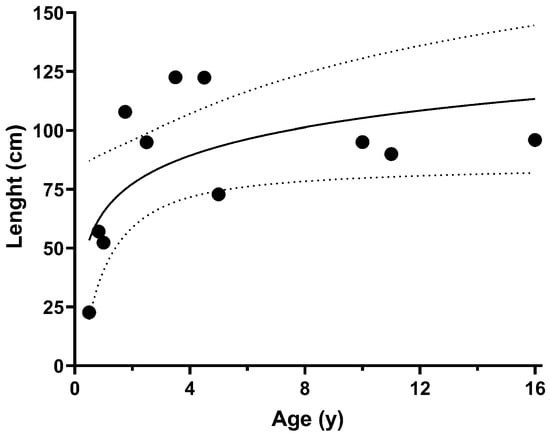
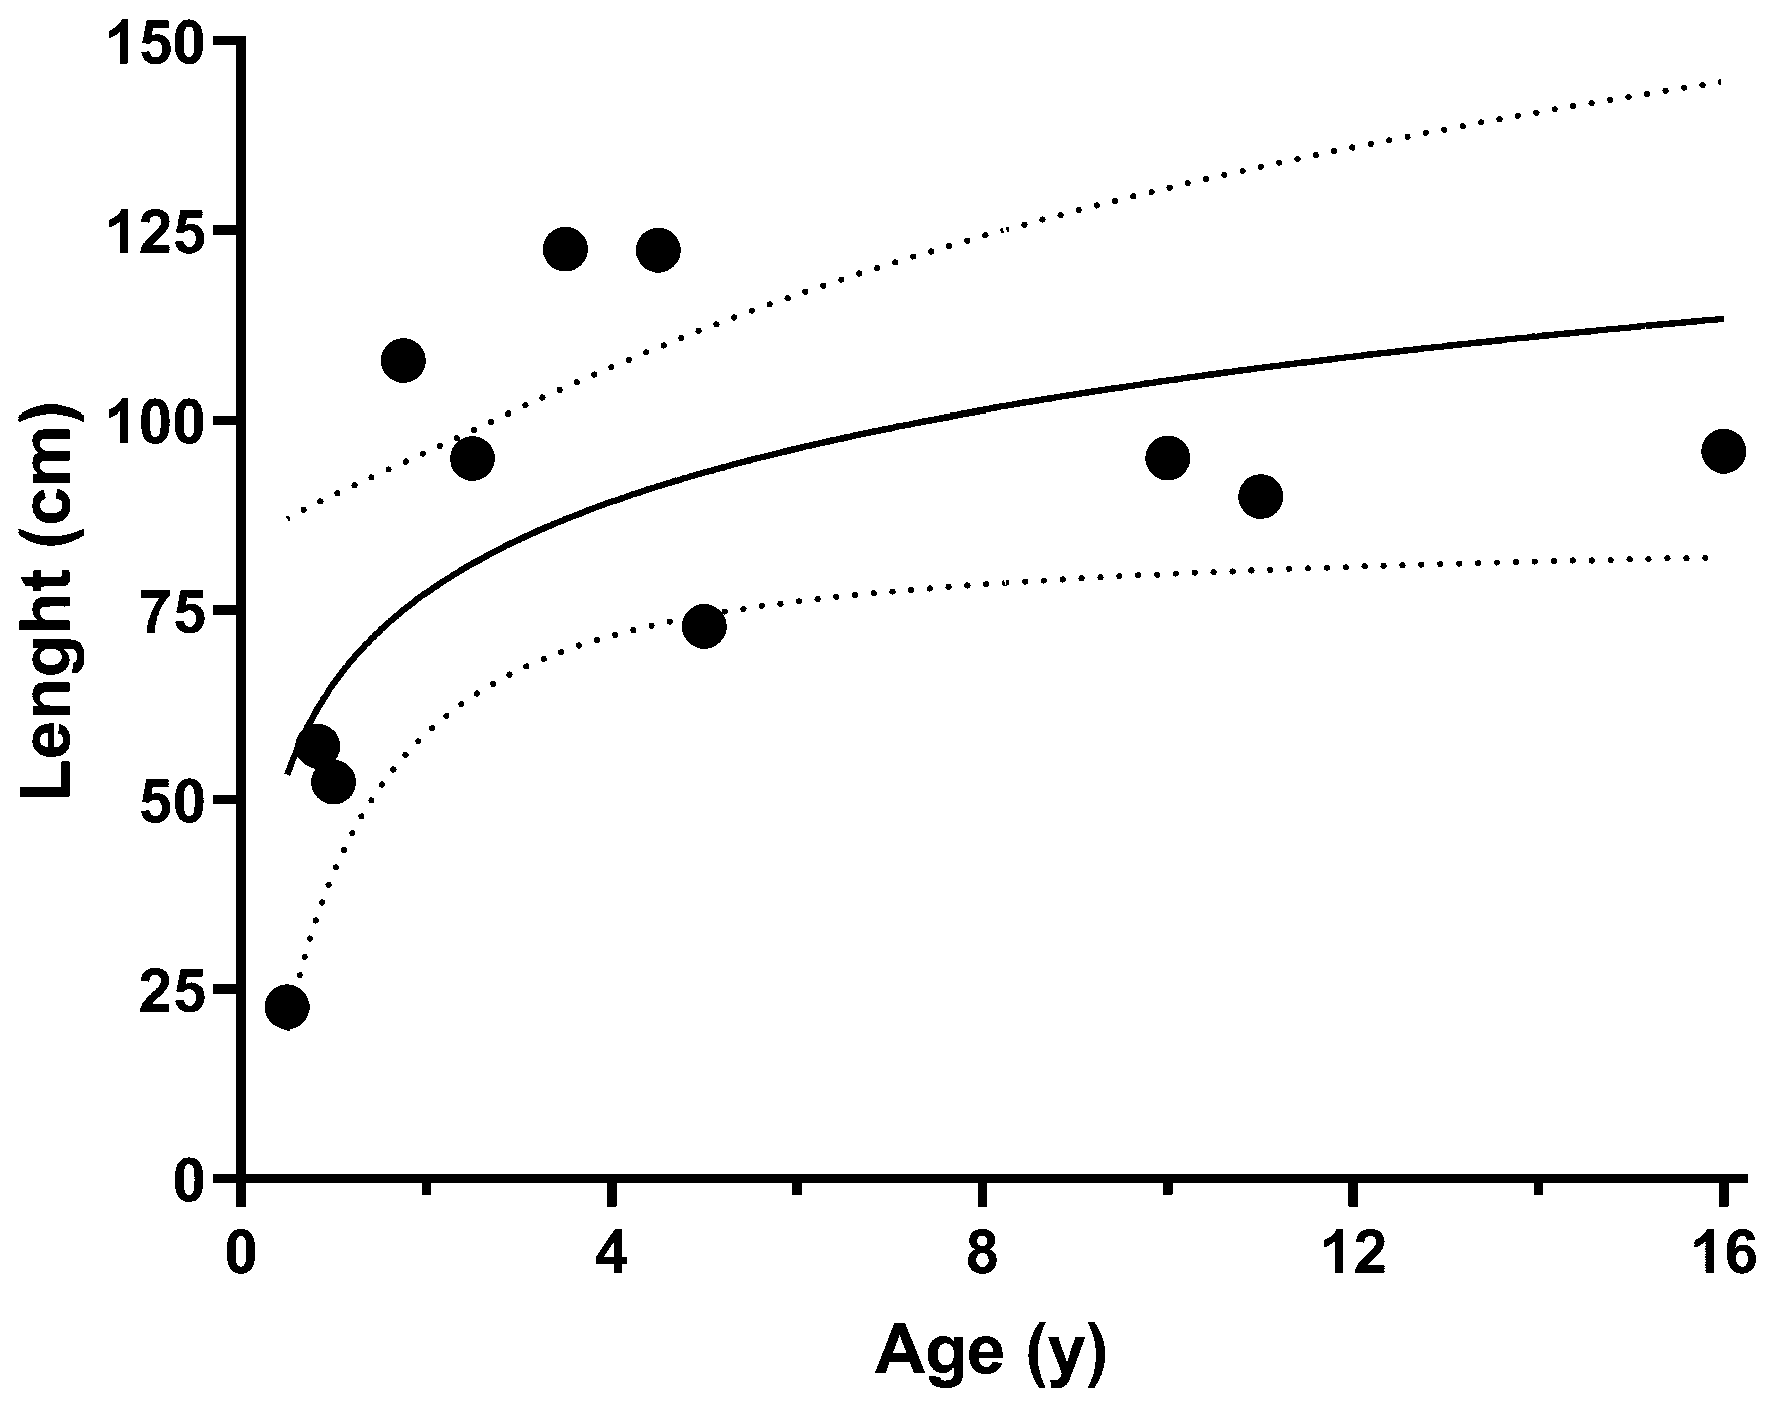
Fewer values were available for the mean length of the pediatric colon, with the values mostly reflecting the total colon. This is plotted against the age of the children in Figure 8, showing a semi-log increase in total colon length with age (R2 = 0.4012, p < 0.0333).
Figure 8.
Mean pediatric total colon length of the colon extracted from the reviewed literature plotted against the corresponding mean age. The solid line indicates the best semi-logarithmic fit (R2 = 0.4012, p < 0.0333) and the dotted lines the 95% confidence interval.
4. Discussion
The data from the 31 publications identified and reviewed here provided a new comprehensive picture of current knowledge of the length of the human colon and of its anatomical segments.
The body of data reviewed originates from many studies using very different techniques and spanning over a century. They include different populations, different ethnicities, and potential functional and neurological confounds. This needs to be taken into account when reflecting on the data and the variability between the measurements, particularly in the meta-analysis. Direct measurements were performed during surgical procedures and on cadavers. A study comparing living subjects and cadavers highlighted marked differences in sigmoid colon lengths, which were 64% longer in living subjects compared with cadavers [29]. However, another study found no marked differences between living and cadaveric sigmoid colon lengths [36]. Comparison between radiographic studies and postmortem studies also showed differences, but with postmortem lengths being higher than for radiographic studies [31]. Some of these differences may be due to postmortem/positional changes compared with the living organ in situ. Radiographic studies are also limited to two-dimensional projections of the organs, which do not reflect antero-posterior dimensions, which can introduce larger errors for the distal part of the colon. By contrast, cross-sectional medical imaging techniques can provide a better three-dimensional appraisal of the colon. Colonoscopy measures may depend on the maneuvering technique used to pass the camera catheter through the colon, which could yield underestimated measures of length, and in some reports, CTC was shown to overestimate colon length compared with colonoscopy [22,24]. The use of barium enemas and of CT luminal contrast are not physiological and may also affect the morphology before measurement. Drugs used for colonoscopy and anesthetics used for surgical procedures may also increase colon length. MRI in the undisturbed colon was a more recent addition to the above techniques [2,7]. Colonoscopy studies provide direct visualization of the colon and are commonly used for diagnostic and therapeutic purposes. While they offer real-time assessments of colon length, they may be subject to measurement errors and variations in procedural techniques. Magnetic endoscopic imaging (MEI) studies offer novel approaches to colonoscopy, allowing for enhanced visualization and measurement accuracy, particularly in challenging cases such as acromegaly. However, they may require specialized equipment and expertise, limiting their widespread applicability.
The meta-analysis performed here provided novel insights on the length of the colon and of its segments. The key messages were not only the actual mean values but also the large variability in lengths, with coefficients of variation between 19% and 39%. The greatest variability was seen in the sigmoid colon, most likely due to the fact that it is the most tortuous and is more difficult to image and assess. It is important to note that some of the variability in the measurement is also possibly originating from the different techniques and confounds mentioned above. Future research using state-of-the-art non-invasive techniques will be able to refine such data and is likely to reduce this variability.
Several studies indicated that colon length in adult males was longer than that in adult females, ranging between 4% and 18% longer [10,11,20,35] whilst others found no such differences [13,18] or the opposite difference [23,25], with the transverse colon being longer in females [15], which could be possibly due to case selection. Colon length also showed some functional association, with the colon in patients with constipation reported to be longer compared with people with normal bowel habits [2,27].
A better understanding of colon lengths and sex [25] or ethnic [34] differences may allow a better estimation of the likely ease of colonoscopy procedures, with increased lengths in the rectum, sigmoid, and total colon having been observed amongst patients with challenging incomplete procedures [12,14,15,21,24]. The demonstration of the varying length of the different segments supports previous impressions that the transverse colon is the longest segment and the most variable. This adds to our understanding of its key storage function. The large and variable size allows the accommodation of variable inputs to ensure regular bowel habits despite variable inputs being related to a differing intake of bulking agents like dietary fiber.
5. Conclusions
The data summarized here contribute to our understanding of colon morphology and may also have implications for clinical practice, particularly for colonoscopy and preoperative planning of surgical resections. It also has the potential to improve our understanding of anatomical correlates of functional diseases such as diarrhea and constipation. This work also highlighted the need for more standardized measurement protocols. There are much fewer studies on the colon in children and young adults and this should be a zone of focus for further research. Non-invasive, non-destructive imaging techniques such as MRI can provide more physiologically relevant measurements of colon length.
Author Contributions
F.A.—conceptualization, data collection, literature analysis, analysis and interpretation of results, and manuscript preparation; T.A.—literature analysis, analysis and interpretation of results, and manuscript preparation; H.F.—literature analysis, analysis and interpretation of results, and manuscript preparation; S.K.—interpretation of results and manuscript preparation; C.L.H.—interpretation of results and manuscript preparation; R.C.S.—interpretation of results and manuscript preparation; M.A.T.—supervision, interpretation of results, and manuscript preparation; L.M.—supervision, conceptualization, data collection, literature analysis, analysis and interpretation of results, and manuscript preparation. All authors have read and agreed to the published version of the manuscript.
Funding
F.A. was funded by a Ph.D. scholarship from King Saud Medical City, Saudi Arabia. This work was supported by the National Institute for Health and Care Research (NIHR) Nottingham Biomedical Research Centre. The views expressed are those of the authors and not necessarily those of the NHS, the NIHR, or the Department of Health & Social Care.
Institutional Review Board Statement
Ethical approval was not necessary for the preparation of this article.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors do not declare any financial or personal links with other persons or organizations that might adversely affect the content of the publication or claim any right to the publication. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript, or in the decision to publish the results.
References
- Bharucha, A.E.; Camilleri, M. Physiology of the colon and its measurement. In Shackelford’s Surgery of the Alimentary Tract, 2 Volume Set; Elsevier: Amsterdam, The Netherlands, 2019; pp. 1676–1688. [Google Scholar]
- Sharif, H.; Hoad, C.L.; Abrehart, N.; Gowland, P.A.; Spiller, R.C.; Kirkham, S.; Loganathan, S.; Papadopoulos, M.; Benninga, M.A.; Devadason, D. Colon length in pediatric health and constipation measured using magnetic resonance imaging and three dimensional skeletonization. PLoS ONE 2024, 19, e0296311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hounnou, G.; Destrieux, C.; Desmé, J.; Bertrand, P.; Velut, S. Anatomical study of the length of the human intestine. Surg. Radiol. Anat. 2002, 24, 290–294. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raahave, D.; Christensen, E.; Loud, F.B.; Knudsen, L.L. Correlation of bowel symptoms with colonic transit, length, and faecal load in functional faecal retention. Dan. Med. Bull. 2009, 56, 83–88. [Google Scholar] [PubMed]
- Yik, Y.I.; Cook, D.J.; Veysey, D.M.; Tudball, C.F.; Cain, T.M.; Southwell, B.R.; Hutson, J.M. How common is colonic elongation in children with slow-transit constipation or anorectal retention? J. Pediatr. Surg. 2012, 47, 1414–1420. [Google Scholar] [CrossRef] [Scilit]
- Flor, N.; Martinelli, A.; Maconi, G.; Di Pietro, S.; Perillo, N.; Maggi, L. CT colonography evaluation of the relationship between colon anatomy and diverticula. Br. J. Radiol. 2020, 93, 20200670. [Google Scholar] [CrossRef] [Scilit]
- Mark, E.B.; Poulsen, J.L.; Haase, A.M.; Frokjaer, J.B.; Schlageter, V.; Scott, S.M.; Krogh, K.; Drewes, A.M. Assessment of colorectal length using the electromagnetic capsule tracking system: A comparative validation study in healthy subjects. Colorectal Dis. 2017, 19, O350–O357. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G.; The PRISMA Group. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. Ann. Intern. Med. 2009, 151, 264–269. [Google Scholar] [CrossRef]
- Modesti, P.A.; Reboldi, G.; Cappuccio, F.P.; Agyemang, C.; Remuzzi, G.; Rapi, S.; Perruolo, E.; Parati, G.; ESH Working Group on CV Risk in Low Resource Settings. Panethnic differences in blood pressure in Europe: A systematic review and meta-analysis. PLoS ONE 2016, 11, e0147601. [Google Scholar] [CrossRef] [Scilit]
- Treves, F. Lectures on the anatomy of the intestinal canal and peritoneum in man. Br. Med. J. 1885, 1, 470. [Google Scholar] [CrossRef] [Scilit]
- Underhill, B.M. Intestinal length in man. Br. Med. J. 1955, 2, 1243–1246. [Google Scholar] [CrossRef] [Scilit]
- Saunders, B.P.; Halligan, S.; Jobling, C.; Fukumoto, M.; Moussa, M.E.; Williams, C.B.; Bartram, C.I. Can barium enema indicate when colonoscopy will be difficult? Clin. Radiol. 1995, 50, 318–321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saunders, B.P.; Phillips, R.K.S.; Williams, C.B. Intraoperative measurement of colonic anatomy and attachments with relevance to colonoscopy. Br. J. Surg. 1995, 82, 1491–1493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saunders, B.P.; Fukumoto, M.; Halligan, S.; Jobling, C.; Moussa, M.E.; Bartram, C.I.; Williams, C.B. Why is colonoscopy more difficult in women? Gastrointest. Endosc. 1996, 43, 124–126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rowland, R.S.; Bell, G.D.; Dogramadzi, S.; Allen, C. Colonoscopy aided by magnetic 3D imaging: Is the technique sufficiently sensitive to detect differences between men and women? Med. Biol. Eng. Comput. 1999, 37, 673–679. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Renehan, A.G.; Painter, J.E.; Bell, G.D.; Rowland, R.S.; O’Dwyer, S.T.; Shalet, S.M. Determination of large bowel length and loop complexity in patients with acromegaly undergoing screening colonoscopy. J. Clin. Endocrinol. Metab. 2005, 62, 323–330. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Punwani, S.; Halligan, S.; Tolan, D.; Taylor, S.A.; Hawkes, D. Quantitative assessment of colonic movement between prone and supine patient positions during CT colonography. Br. J. Radiol. 2009, 82, 475–481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phillips, M.; Patel, A.; Meredith, P.; Will, O.; Brassett, C. Segmental colonic length and mobility. Ann. R. Coll. Surg. Engl. 2015, 97, 439–444. [Google Scholar] [CrossRef] [Scilit]
- Alazmani, A.; Hood, A.; Jayne, D.; Neville, A.; Culmer, P. Quantitative assessment of colorectal morphology: Implications for robotic colonoscopy. Med. Eng. Phys. 2016, 38, 148–154. [Google Scholar] [CrossRef] [Scilit]
- Bryant, J. Observation upon the growth and length of human intestine. Am. J. Med. Sci. 1924, 167, 499–519. [Google Scholar] [CrossRef] [Scilit]
- Hanson, M.E.; Pickhardt, P.J.; Kim, D.H.; Pfau, P.R. Anatomic factors predictive of incomplete colonoscopy based on findings at CT colonography. Am. J. Roentgenol. 2007, 189, 774–779. [Google Scholar] [CrossRef] [Scilit]
- Duncan, J.E.; McNally, M.P.; Sweeney, W.B.; Gentry, A.B.; Barlow, D.S.; Jensen, D.W.; Cash, B.D. CT colonography predictably overestimates colonic length and distance to polyps compared with optical colonoscopy. Am. J. Roentgenol. 2009, 193, 1291–1295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khashab, M.; Pickhardt, P.J.; Kim, D.H.; Rex, D.K. Colorectal anatomy in adults at CT colonography: Normal distribution and the effect of age, gender, and body mass index. Gastrointest. Endosc. 2009, 69, AB275. [Google Scholar] [CrossRef] [Scilit]
- Eickhoff, A.; Pickhardt, P.J.; Hartmann, D.; Riemann, J.F. Colon anatomy based on CT colonography and fluoroscopy: Impact on looping, straightening and ancillary manoeuvres in colonoscopy. Dig. Liver Dis. 2010, 42, 291–296. [Google Scholar] [CrossRef] [Scilit]
- Sadahiro, S.; Ohmura, T.; Yamada, Y.; Saito, T.; Taki, Y. Analysis of length and surface area of each segment of the large intestine according to age, sex and physique. Surg. Radiol. Anat. 1992, 14, 251–257. [Google Scholar] [CrossRef] [Scilit]
- Ohgo, H.; Imaeda, H.; Yamaoka, M.; Yoneno, K.; Hosoe, N.; Mizukami, T.; Nakamoto, H. Irritable bowel syndrome evaluation using computed tomography colonography. World J. Gastroenterol. 2016, 22, 9394–9399. [Google Scholar] [CrossRef] [Scilit]
- Utano, K.; Nagata, K.; Honda, T.; Kato, T.; Lefor, A.K.; Togashi, K. Bowel habits and gender correlate with colon length measured by CT colonography. Jpn. J. Radiol. 2022, 40, 298–307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sadahiro, S.; Ohmura, T.; Saito, T.; Suzuki, S. Relationship between length and surface-area of each segment of the large intestine and the incidence of colorectal cancer. Cancer 1991, 68, 84–87. [Google Scholar] [CrossRef] [Scilit]
- Bhatnagar, B.N.S.; Sharma, C.L.N.; Gupta, S.N.; Mathur, M.M.; Reddy, D.C.S. Study on the anatomical dimensions of the human sigmoid colon. Clin. Anat. 2004, 17, 236–243. [Google Scholar] [CrossRef] [Scilit]
- Michael, S.A.; Rabi, S. Morphology of Sigmoid Colon in South Indian Population: A Cadaveric Study. J. Clin. Diagn. Res. 2015, 9, AC04–AC07. [Google Scholar] [CrossRef] [Scilit]
- Chapuis, P.H.; Faithfull, G.R.; Dent, O.F. Large bowel segment lengths and the distribution of colorectal cancer. Aust. N. Z. J. Surg. 1982, 52, 385–390. [Google Scholar] [CrossRef] [Scilit]
- Bayeh, A.B.; Abegaz, B.A. The role of sigmoid colon anatomic dimensions in the development of sigmoid volvulus, North-Western Ethiopia. PLoS ONE 2021, 16, e0260708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mirjalili, S.A.; Tarr, G.; Stringer, M.D. The length of the large intestine in children determined by computed tomography scan. Clin. Anat. 2017, 30, 887–893. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Madiba, T.E.; Haffajee, M.R.; Sikhosana, M.H. Radiological anatomy of the sigmoid colon. Surg. Radiol. Anat. 2008, 30, 409–415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Struijs, M.C.; Diamond, I.R.; de Silva, N.; Wales, P.W. Establishing norms for intestinal length in children. J. Pediatr. Surg. 2009, 44, 933–938. [Google Scholar] [CrossRef] [Scilit]
- Alatise, O.I.; Ojo, O.; Nwoha, P.; Omoniyi-Esan, G.; Omonisi, A. The role of the anatomy of the sigmoid colon in developing sigmoid volvulus: A cross-sectional study. Surg. Radiol. Anat. 2013, 35, 249–257. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).