


Abstract
Background Cerebral autosomal dominant arteriopathy with subcortical infarcts and leukoencephalopathy (CADASIL) is an autosomal dominant neurological disorder caused by mutations in the NOTCH3 gene. Disease-causing variants in NOTCH3 are primarily missense variants altering the number of cysteine residues in the translated NOTCH3 protein. The genetic screening of the NOTCH3 gene is currently considered the gold standard for CADASIL diagnosis. Methods The Genomics Research Centre has been performing diagnostic genetic testing for CADASIL since 1997. A total of 1281 patient samples suspected of having CADASIL were screened for NOTCH3 mutations from January 1, 1997, to October 1, 2025. Genomic sequencing was performed using Sanger sequencing of selected NOTCH3 exons or using next-generation sequencing to screen the entire NOTCH3 gene. Results In total, 12.1% of patients had a cysteine-altering NOTCH3 variant, including 49 variants in exons 2-24, and two variants in non-EGFr encoding exons. We also report the first CADASIL patient who is a compound heterozygote for two known pathogenic cysteine-altering NOTCH3 variants, who presented with a severe early onset of stroke, migraine, and white matter changes. Conclusions The compound heterozygosity identified in this patient appears to be associated with an early onset of CADASIL symptoms. Our study contributes to the elucidation of the spectrum of NOTCH3 variants associated with CADASIL. The majority of patients tested for CADASIL in this study did not contain a variant in NOTCH3, indicating that there are other genes or genetic variants contributing to disease in these patients.
1. Introduction
Cerebral autosomal dominant arteriopathy with subcortical infarcts and leukoencephalopathy (CADASIL) is a hereditary cerebral small vessel disease (CSVD), recognised as the most common genetic cause of strokes in individuals under 65 years old, and significantly contributes to neurologic deterioration in the elderly population [1,2]. The typical disease progression begins with migraines and characteristic hyperintense white matter lesions in the third to fourth decade of life, followed by ischaemic stroke and/or transient ischaemic events in the fifth decade, subcortical dementia in the sixth decade, and death by the seventh decade [3]. Magnetic resonance imaging (MRI) of affected patients displays leukoencephalopathy and subcortical infarcts typically in the external capsules and anterior pole of the temporal lobe, as well as lacunar infarcts and microhaemorrhages in some cases [4]. CADASIL is caused by heterozygous cysteine-altering variants in the epidermal growth factor-like repeat (EGFr) regions of NOTCH3, which result in the mispairing of cysteine residues and altered disulphide bridge formation [5]. This leads to the abnormal cleavage of the NOTCH3 extracellular domain (ECD), which aggregates in the form of granular osmiophilic material (GOM) [6]. This accumulation of is located adjacent to affected vascular smooth muscle cells (VSMCs), and is pathognomonic for CADASIL when detected in a skin biopsy [7]. It is important to note, however, that pathogenic NOTCH3 variants are not always identified in patients with a positive CADASIL skin biopsy [8]. Conversely, not all individuals carrying a pathogenic NOTCH3 variant exhibit GOM [7,9]. Furthermore, cysteine-sparing variants within NOTCH3 have been detected in GOM-positive patients and, although not typically classified as CADASIL-causing, may contribute to CADASIL pathogenesis [10].
The clinical presentation of CADASIL patients is dependent upon the location of pathogenic variants. NOTCH3 variants in EGFrs 1-6 have been associated with a 13-fold increase in the risk of stroke and vascular dementia compared to control cases, whilst variants in EGFRs 7-34 display a greater than 2-fold risk compared to healthy individuals [11]. Phenotypic variability in CADASIL is prominent; however, the age of onset and severity of symptoms often differ significantly between variants and within families [12]. While the majority of CADASIL-causing mutations are heterozygous, a small number of homozygous and compound heterozygous variants have been detected as causative of a CADASIL-like phenotype [13,14].
The Genomics Research Centre at the Queensland University of Technology has performed diagnostic genetic testing for CADASIL since 1997. This work was originally performed using Sanger sequencing of selected exons known to be hotspot regions for CADASIL variants, and was subsequently expanded to include the entirety of the NOTCH3 gene with the advent of next-generation sequencing (NGS) [14,15]. This resulted in an improvement in diagnostic rate of CADASIL variant detection of 5%, as previously described by our laboratory [14]. The current study analyses the spectrum of NOTCH3 variants identified in a large cohort of 1281 suspected CADASIL patients.
2. Materials and Methods
2.1. Patient Cohort
Patients were originally referred to the Genomics Research Centre NATA (National Association of Testing Authorities, Australia) accredited diagnostic laboratory by physicians in Australia and New Zealand. Patients were referred based upon a clinical suspicion of CADASIL or monogenic CSVD with a history of acute or lacunar stroke, vascular dementia, MRI features of CSVD (white matter hyperintensities, lacunes), migraine, and/or family history of stroke, vascular dementia, or small vessel disease. Ethical approval for these studies is through QUT HREC (Approval Number 1400000748). Patient results were selected from internal de-identified records from 1 January 1997 to 1 October 2025. Patients were excluded if they were family members of previously investigated probands with a confirmatory result.
2.2. Sanger Sequencing
Sanger sequencing was initially performed on exons 3 and 4, or an extended analysis including exons 2, 11, 18, and 19. All exons selected for analysis were based on identified mutational hotspots in NOTCH3 (NM_000435.2). The primer sets were designed to encompass the entire exon examined and extend into the surrounding introns, resulting in amplicons of the following sizes: 193 bp (exon 2), 296 bp (exon 3), 488 bp (exon 4), 367 bp (exon 11), 258 bp (exon 18), 350 bp (exon 19) (Table S1) [16]. The methods used for NOTCH3 Sanger sequencing were performed as previously described by Dunn et al., 2020 [14]. Samples were sequenced using the Thermo Fisher BigDye™ Terminator v3.1 Cycle Sequencing Kit (Thermo Fisher Scientific, Scoresby, VIC, Australia) and were analysed following separation on an Applied Biosystems™ 3500 Genetic Analyzer (Thermo Fisher Scientific, Scoresby, VIC, Australia).
2.3. Next-Generation Sequencing
NGS was conducted using an Ion AmpliSeq Custom NGS panel. The panel initially contained five genes associated with neurological disorders (CACNA1A, ATP1A2, SCN1A, NOTCH3, TRESK), and was expanded to include ten additional migraine or CSVD-associated genes (TREX1, FOXC1, HTRA1, KCNA1, COL4A1, COL4A2, PRRT2, SCN2A, ATP1A3, GLA) [14,17]. The patient’s peripheral blood was used to extract genomic DNA (gDNA) using the QIAamp DNA Blood Mini Kit via the automated QIAcube (QIAGEN, VIC, Australia). Library preparation was performed using the Ion AmpliSeq Library Kit 2.0 (Thermo Fisher Scientific, Scoresby, VIC, Australia). Sequencing was performed on the Ion GeneStudio S5 plus platform (Thermo Fisher Scoresby, VIC, Australia), using the Ion 550 Chip, with data analysed through the Ion Torrent suite v5.10. The generated variant call format (VCF) file for the patient sample was exported into the data analysis software, Ion Reporter v5.12 (Thermo Fisher Scientific, Scoresby, VIC, Australia) [15].
2.4. Bioinformatic Analysis
The results generated in the Ion Reporter utilised functional analyses such as in silico variant predictors, minor allele frequency (MAF), the type of variant (coding, non-coding), and amino acid changes (if applicable). Notable variant(s) were selected for further analysis based on predefined parameters: (i) the variant is coding or in a known region of pathogenicity; (ii) the variant is amino acid changing or predicted to alter protein product; (iii) the minor allele frequency (MAF) of the variant is less than 0.001; and (iv) multiple in silico predictors labelled the variant as pathogenic or likely pathogenic. These parameters were cross-referenced with various databases, multiple in silico variant effect predictors, and available literature for variant curation according to the American College of Medical Genetics (ACMG) guidelines [18].
3. Results
Diagnostic testing of NOTCH3 was performed for 407 patients by Sanger sequencing and 874 patients by NGS of the complete NOTCH3 gene. Fifty-one unique variants were identified in 155 patients across a total of 1281 patient samples, yielding an overall diagnostic rate of 12.1% (Table S2). Of these, 44 cases were detected by targeted Sanger sequencing of selected exons, while the remainder were identified through NGS of the entire NOTCH3 gene. In total, 49 variants were identified as disease causing, all of which were cysteine-altering (Table S2). Two cysteine-altering variants were detected in this study and classified as variants of uncertain significance (VUS) (Table S3). These variants, p.Arg1483Cys & p.Arg2150Cys, were found in exons 25 and 33, respectively. Both variants are rare in population databases (MAF < 0.000022) but are predicted to be benign by the majority of in silico tools (Table S3). Overall, 98.7% of all detected variants were located within exons 2–24 of NOTCH3.
Clinical and demographic characteristics were compared between individuals carrying NOTCH3 variants located in EGFr domains 1-6 and those in domains 7-34 (Table 1). Overall, variants were more frequently identified in females, who were on average older at the time of assessment than males. A greater number of individuals carried variants within EGFr 1-6 compared to EGFr 7-34; however, no significant differences were observed between groups in the occurrence of clinical or radiological features.
Table 1.
Comparison of Clinical and Radiological Features in NOTCH3 Variant Carriers by EGFr Domain.
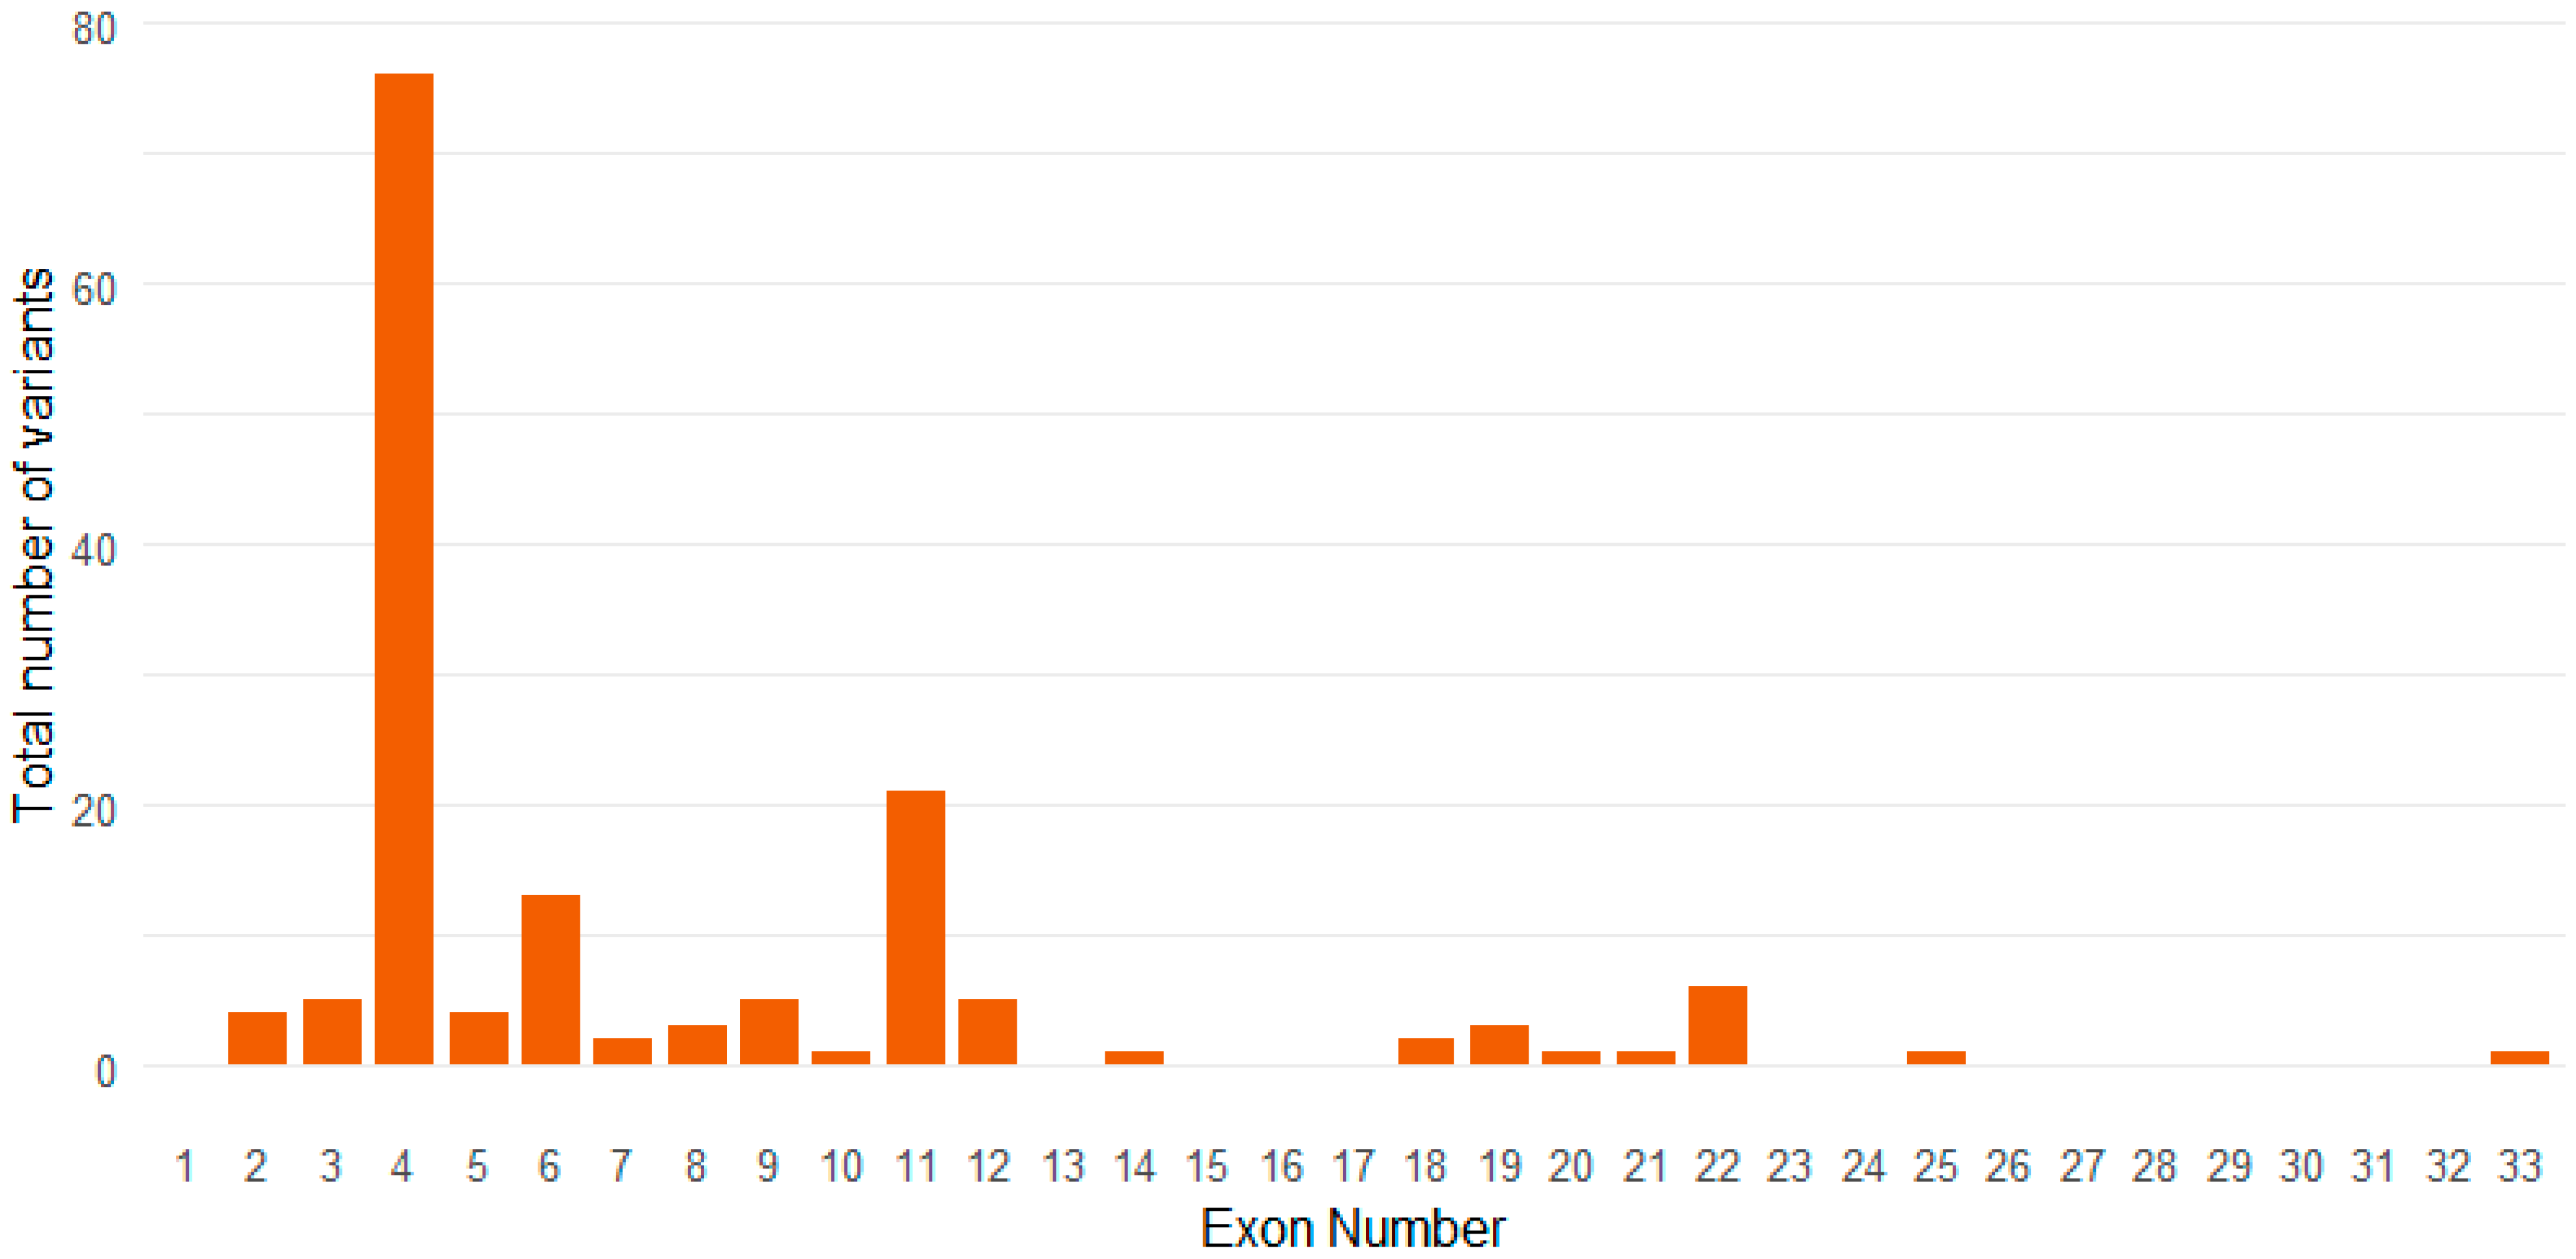
The most common exonic locations of variants in this cohort were exon 4, exon 6, and exon 11 (Figure 1). The most common disease-causing variants identified in our cohort were p.Arg141Cys (n = 25/155, 16.1%), p.Arg153Cys (n = 12/155, 7.7%), and p.Arg182Cys (n = 18/155, 11.6%), each of which was located in exon four, which is the most common location for pathogenic NOTCH3 variants.
Figure 1.
Location of NOTCH3 Variants Stratified by Exon.
All variants identified in our cohort were present in a heterozygous state except for two patients. One patient was identified to possess a homozygous cysteine-altering variant, p.Arg587Cys, located in exon 11 of NOTCH3, in the EGFr region 15 [14]. An additional patient was determined to have two disease-causing variants, p.Arg110Cys and p.Arg1231Cys, in a compound heterozygous state. The presence of both heterozygous variants was confirmed via Sanger sequencing (Figure S1). The p.Arg110Cys variant is located in exon 3, EGFr region 2, and the p.Arg1231Cys variant is located in exon 22, EGFr region 31.
The p.Arg110Cys mutation is well established within the literature as a mechanism of CADASIL pathogenesis. In a population study of NOTCH3 variants, only one Caucasian individual in the UK Biobank was found to harbour this variant, however this individual is likely young enough to be asymptomatic as CADASIL is a late-onset disorder [19]. The p.Arg1231Cys variant has been detected in numerous CADASIL studies as causative of disease [20,21]. Analysis of NOTCH3 cysteine-altering variants in both the Geisinger DiscovEHR and UK Biobank cohort revealed that p.Arg1231Cys was the most common variant within the EGFr 7-34 domains [22,23,24]. In our clinical cohort, these variants have been identified individually three (p.Arg110Cys) and four (p.Arg1231Cys) times, respectively.
This 35-year-old female patient with a history of migraine had experienced two ischaemic strokes at ages 30 and 33. Brain MRI following the initial event revealed extensive T2 hyperintensities in temporal poles, suggestive of CADASIL. After the second ischaemic stroke in 2022, a skin biopsy confirmed the presence of GOM on electron microscopy. A follow-up MRI in 2023 demonstrated focal areas of increased signal intensity in the centrum semiovale and subcortical white matter, predominantly in the frontal lobes, with evidence of lacunar infarcts. Neuropsychological assessment revealed preserved cognitive and executive function but noted reductions in psychomotor processing speed and performance on complex tasks. The patient had no known cardiovascular risk factors, psychiatric history, or family history of neurological disorders or dementia. Neither parent was available for clinical evaluation or genetic testing; however, both were reportedly asymptomatic, with no history suggestive of CADASIL.
4. Discussion
CADASIL is the most common inherited monogenic cause of stroke and dementia worldwide. To date, 246 pathogenic variants have been described in the EGFR regions of NOTCH3, with 95% being identified as missense variants altering cysteine residues [3,25]. While the exact mechanisms of CADASIL pathogenesis are unknown, variants resulting in loss of function and gain of function have been identified to cause CADASIL-like phenotypes [26]. Monoallelic cysteine-altering variants have been shown to result in a toxic gain of function, where disruption in disulphide bridge formation leads to the formation of GOM around VSMCs and brain pericytes, producing toxic effects on neighbouring cells [27]. These include reduced VSMC proliferation, increased production of reactive oxygen species, impaired degradation of mutant NOTCH3 proteins, and activation of stress responses within cells [28,29].
In the current study, the majority of variants (n = 153/155; 98.7%) were located in exons 2-24 of NOTCH3, which encode the EGFr domains critical for disulphide bridge formation, consistent with the established disease model [30]. Of these, all variants identified as disease-causing were cysteine-altering, causing an imbalance in the number of cysteine residues, leading to disrupted disulphide bond formation. A greater number of variants were identified in early EGFr regions in this cohort, likely due to the more severe phenotype and earlier onset of disease associated with variants in these domains, as opposed to the milder severity and later onset of variants in EGFr regions 7-34 [31]. No significant differences were identified in clinical or radiological features between EGFr groups. This may be due to the later age at presentation of patients with EGFr 7-34 variants, which may still be fully penetrant, and thus result in similar clinical presentation [20]. Additionally, complete phenotype information was not available for all patients, potentially impacting the genotype-phenotype correlation in this study. This also precludes the potential for exon-specific or variant-specific analysis of phenotypes.
Two cysteine-altering variants were classified as variants of uncertain significance (VUS) in this study.
These cysteine-altering variants were identified in exons 25-33 of NOTCH3, which encode the extracellular domain but lie outside the EGFr-encoding regions [10,32]. Although these exons are not classically associated with CADASIL, variants within this region have been reported in individuals with a clinical CADASIL phenotype and may be impact the structural stability of the NOTCH3 homodimer [32]. Further, loss-of-function variants in this region have been associated with CADASIL-like syndromes presenting at a much earlier age ranging from congenital onset to 17 years of age, with prominent neurodevelopmental features, including developmental delay, intellectual disability, and dysmorphic features [13]. These findings suggest that variants in exon 25-33 may contribute to CADASIL or CADASIL-like phenotypes, despite differing from the classical mutation profile.
Homozygosity and compound heterozygosity for NOTCH3 missense variants have also been reported in the literature; however, it is exceedingly rare, with fewer than 20 cases reported to date [13,30,33]. Several reports describe homozygous missense variants in NOTCH3, most frequently p.Arg1231Cys in exon 22 (EGFr 31) [13]. Within our laboratory, we identified one homozygous variant, p.Arg587Cys, located in exon 11 (EGFr 15). However, the phenotype observed in this patient did not differ significantly from that seen in heterozygous cases. Overall, the majority of homozygous variants in the literature are located within EGFRs 7-34 in NOTCH3 and are associated with a classical CADASIL phenotype, with no notable difference in age of onset or disease severity compared to individuals with the corresponding heterozygous variant [34,35,36,37,38]. Notably, only two cases have been reported with homozygous variants located in EGFR regions 1-6 (p.Arg133Cys & p.Cys183Ser), both of which were associated with an earlier and more severe CADASIL phenotype as compared to heterozygous carriers [39,40].
To our knowledge, the compound heterozygous genotype identified in the patient described here represents the first reported case involving a cysteine-altering variant within EGFr domains 1-6 in combination with another cysteine-altering variant in the EGFr regions of NOTCH3. All other compound heterozygote cases within the literature have been identified to affect EGFr regions 7-34 or in combination with cysteine-sparing variants [30]. Additionally, these cases have not been associated with a significantly different phenotype compared to monoallelic carriers, with a reported mean age at symptom onset of 43 years [13].
Our findings suggest that when present with another cysteine-altering variant, mutations located within the early EGFr regions of NOTCH3 may contribute to a more severe CADASIL phenotype. This observation aligns with previously reported cases of homozygous variants identified in early EGFrs, which have been associated with increased disease severity. A high degree of inter-individual expressivity has been noted in CADASIL patients, both between variant positions and within families carrying the same variant.
It is likely that the p.Arg110Cys variant identified in this patient drives the phenotype expressed in this patient due to its position in a high-risk EGFr and known role as causative of a strong CADASIL phenotype [32]. However, the phenotype observed in the current patient may be influenced by unknown genetic interactions arising from this novel compound heterozygous genotype, or by additional genetic or environmental modifiers contributing to disease expression. However, further investigation is required, and a larger number of CADASIL patients with biallelic variants affecting early EGFrs in NOTCH3 need to be studied before a definitive conclusion can be drawn. The inability to phase the compound heterozygous genotype identified within the patient due to an inability to perform familial segregation limits the interpretability of these variants, particularly with respect to potential inheritance of the disorder in the patient’s children.
In summary, pathogenic or likely pathogenic variants were identified in only 12.1% of patients in this study, indicating that other potential causes of disease or genetic factors need to be considered in the diagnosis of CADASIL.
5. Conclusions
This study defines the mutational spectrum of NOTCH3 variants in a large clinical CADASIL cohort, demonstrating that the majority of variants occur within exons 2-24 and that cysteine-altering variants remain the primary known genetic cause of disease in these patients. The majority of patients suspected of CADASIL did not contain causal variants in NOTCH3, indicating that there are unknown genetic factors causing disease in these patients. The detection of two cysteine-altering missense variants in a 35-year-old female patient who presented with two ischaemic events, white matter hyperintensities, and microvascular changes on MRI highlights the role of complex inheritance in CADASIL pathogenesis. The early disease onset and severity observed in this case may reflect the cumulative deleterious effect of multiple disease-causing variants, offering further insight into the mechanisms underlying phenotypic variability in CADASIL.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/genes16111353/s1, Figure S1: Sequence traces (reverse complement) of the two cysteine-altering variants in NOTCH3 identified by NGS. p.Arg110Cys variant (left) and p.Arg1231Cys variant (right) with Sanger chromatogram (top) and Integrated Genomics Viewer (IGV, bottom) indicating heterozygous mutations; Table S1: Primer Sequences used for PCR amplification of NOTCH3 exons for Sanger sequencing. Primer sequences are written in the 5′-3′ direction; Table S2: NOTCH3 Cysteine altering variants (n = 51) identified from Sanger and next-generation sequencing according to exon, epidermal growth factor-like repeat (EGFR) region, and number of samples containing each variant, including variants previously described by Dunn et al. (2020) [14]. NOTCH3 assembly: NM_000435.3. ACMG: American College of Medical Genetics. ‘+’ = known pathogenic mechanism, ‘-‘ = not previously characterised; Table S3: In silico and Population Frequency Data for NOTCH3 Variants of Uncertain Significance. NOTCH3 transcript: NM_000435.3. Minor allele frequencies (MAF) were obtained from the GnomAD v4.1.0 total dataset. P = Pathogenic, LP = Likely Pathogenic, VUS = Variant of Uncertain Significance.
Author Contributions
Conceptualization, S.K.G., N.M., H.G.S. and L.R.G.; Formal analysis, S.K.G., J.T., N.M., R.A.S. and H.G.S.; Methodology, S.K.G., J.T., N.M., R.A.S., H.G.S., E.H. and A.D.; Visualization, S.K.G., N.M. and H.G.S.; Writing—original draft, S.K.G. and J.T.; Writing—review & editing, S.K.G., N.M., R.A.S., H.G.S., E.H., A.D. and L.R.G. All authors have read and agreed to the published version of the manuscript.
Funding
The authors disclose receipt of the following financial support for this article’s research, authorship, and publication. This work was supported by the Australian National Health and Medical Research Council [NHMRC--APP1122387] (LRG) and by infrastructure purchased with Australian Government EIF Super Science Funds as part of the Therapeutic Innovation Australia—Queensland Node project (LRG); and by a Queensland University of Technology Postgraduate Research Award [QUTPRA].
Institutional Review Board Statement
The study was approved by the Human Research Ethics Committee of the Queensland University of Technology (approval number: 7416, approval date: 14 May 2024), with appropriate written consent obtained from the patient, and in accordance with the Declaration of Helsinki. Diagnostic genetic testing was conducted under National Association of Testing Authorities (NATA) accreditation (accreditation number 14979).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The original contributions presented in this study are included in the article/supplementary material. Further inquiries can be directed to the corresponding author.
Acknowledgments
The authors would like to sincerely thank all patients for their participation in this study. We extend our gratitude to the clinicians, genetic counsellors, and laboratory staff whose contributions were essential to data collection, diagnostic support, and variant interpretation. We also acknowledge the support of the Genomics Research Centre at QUT, as well as the hospitals involved in the study.
Conflicts of Interest
The authors have no relevant financial or non-financial interests to declare that are relevant to the contents of this study.
References
- Young, K.Z.; Xu, G.; Keep, S.G.; Borjigin, J.; Wang, M.M. Overlapping Protein Accumulation Profiles of CADASIL and CAA: Is There a Common Mechanism Driving Cerebral Small-Vessel Disease? Am. J. Pathol. 2021, 191, 1871–1887. [Google Scholar] [CrossRef] [Scilit]
- Mancuso, M.; Arnold, M.; Bersano, A.; Burlina, A.; Chabriat, H.; Debette, S.; Enzinger, C.; Federico, A.; Filla, A.; Finsterer, J.; et al. Monogenic cerebral small-vessel diseases: Diagnosis and therapy. Consensus recommendations of the European Academy of Neurology. Eur. J. Neurol. 2020, 27, 909–927. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sari, U.S.; Kisabay, A.; Batum, M.; Tarhan, S.; Dogan, N.; Coskunoglu, A.; Cam, S.; Yilmaz, H.; Selcuki, D. CADASIL with Atypical Clinical Symptoms, Magnetic Resonance Imaging, and Novel Mutations: Two Case Reports and a Review of the Literature. J. Mol. Neurosci. 2019, 68, 529–538. [Google Scholar] [CrossRef] [Scilit]
- Juhosova, M.; Chandoga, J.; Cisarik, F.; Dallemule, S.; Durina, P.; Jaraskova, D.; Jungova, P.; Kantarska, D.; Kvasnicova, M.; Mistrik, M.; et al. Influence of different spectra of NOTCH3 variants on the clinical phenotype of CADASIL—Experience from Slovakia. Neurogenetics 2023, 24, 1–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joutel, A.; Corpechot, C.; Ducros, A.; Vahedi, K.; Chabriat, H.; Mouton, P.; Alamowitch, S.; Domenga, V.; Cécillion, M.; Maréchal, E.; et al. Notch3 mutations in CADASIL, a hereditary adult-onset condition causing stroke and dementia. Nature 1996, 383, 707–710. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.J.; Zhang, X.; Wu, E.; Sukpraphrute, R.; Sukpraphrute, C.; Ye, A.; Wang, M.M. Structural changes in NOTCH3 induced by CADASIL mutations: Role of cysteine and non-cysteine alterations. J. Biol. Chem. 2023, 299, 104838. [Google Scholar] [CrossRef] [Scilit]
- Cheng, Y.-W.; Chao, C.-C.; Chen, C.-H.; Yeh, T.-Y.; Jeng, J.-S.; Tang, S.-C.; Hsieh, S.-T. Small Fiber Pathology in CADASIL. Clin. Correl. Cogn. Impair. 2022, 99, e583–e593. [Google Scholar] [CrossRef] [Scilit]
- Peters, N.; Opherk, C.; Bergmann, T.; Castro, M.; Herzog, J.; Dichgans, M. Spectrum of Mutations in Biopsy-Proven CADASIL: Implications for Diagnostic Strategies. Arch. Neurol. 2005, 62, 1091–1094. [Google Scholar] [CrossRef] [Scilit]
- Tikka, S.; Mykkänen, K.; Ruchoux, M.M.; Bergholm, R.; Junna, M.; Pöyhönen, M.; Yki-Järvinen, H.; Joutel, A.; Viitanen, M.; Baumann, M.; et al. Congruence between NOTCH3 mutations and GOM in 131 CADASIL patients. Brain 2009, 132, 933–939. [Google Scholar] [CrossRef] [Scilit]
- Cao, Y.; Zhang, D.-D.; Han, F.; Jiang, N.; Yao, M.; Zhu, Y.-C. Phenotypes Associated with NOTCH3 Cysteine-Sparing Mutations in Patients with Clinical Suspicion of CADASIL: A Systematic Review. Int. J. Mol. Sci. 2024, 25, 8796. [Google Scholar] [CrossRef] [Scilit]
- Hack, R.J.; Cerfontaine, M.N.; Gravesteijn, G.; Tap, S.; Hafkemeijer, A.; Grond, J.v.d.; Witjes-Ané, M.-N.; Baas, F.; Rutten, J.W.; Oberstein, S.A.J.L. Effect of NOTCH3 EGFr Group, Sex, and Cardiovascular Risk Factors on CADASIL Clinical and Neuroimaging Outcomes. Stroke 2022, 53, 3133–3144. [Google Scholar] [CrossRef] [Scilit]
- Boston, G.; Jobson, D.; Mizuno, T.; Ihara, M.; Kalaria, R.N. Most common NOTCH3 mutations causing CADASIL or CADASIL-like cerebral small vessel disease: A systematic review. Cereb. Circ. Cogn. Behav. 2024, 6, 100227. [Google Scholar] [CrossRef] [Scilit]
- Iruzubieta, P.; Alves, C.; Al Shamsi, A.M.; ElGhazali, G.; Zaki, M.S.; Pinelli, L.; Lopergolo, D.; Cho, B.P.H.; Jolly, A.A.; Al Futaisi, A.; et al. Clinical and neuroradiological spectrum of biallelic variants in NOTCH3. EBioMedicine 2024, 107, 105297. [Google Scholar] [CrossRef] [Scilit]
- Dunn, P.J.; Maksemous, N.; Smith, R.A.; Sutherland, H.G.; Haupt, L.M.; Griffiths, L.R. Investigating diagnostic sequencing techniques for CADASIL diagnosis. Human Genom. 2020, 14, 2. [Google Scholar] [CrossRef] [Scilit]
- Maksemous, N.; Smith, R.A.; Haupt, L.M.; Griffiths, L.R. Targeted next generation sequencing identifies novel NOTCH3 gene mutations in CADASIL diagnostics patients. Human Genom. 2016, 10, 38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roy, B.; Maksemous, N.; Smith, R.A.; Menon, S.; Davies, G.; Griffiths, L.R. Two novel mutations and a previously unreported intronic polymorphism in the NOTCH3 gene. Mutat. Res. Fundam. Mol. Mech. Mutagen. 2012, 732, 3–8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maksemous, N.; Roy, B.; Smith, R.A.; Griffiths, L.R. Next-generation sequencing identifies novel 1A gene mutations in episodic ataxia type 2. Mol. Genet. Genom. Med. 2016, 4, 211–222. [Google Scholar] [CrossRef] [Scilit]
- Richards, S.; Aziz, N.; Bale, S.; Bick, D.; Das, S.; Gastier-Foster, J.; Grody, W.W.; Hegde, M.; Lyon, E.; Spector, E.; et al. Standards and guidelines for the interpretation of sequence variants: A joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology. Genet. Med. 2015, 17, 405–424. [Google Scholar] [CrossRef] [Scilit]
- Cho, B.P.H.; Nannoni, S.; Harshfield, E.L.; Tozer, D.; Gräf, S.; Bell, S.; Markus, H.S. NOTCH3 variants are more common than expected in the general population and associated with stroke and vascular dementia: An analysis of 200,000 participants. J. Neurol. Neurosurg. Psychiatry 2021, 92, 694–701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rutten, J.W.; Dauwerse, H.G.; Gravesteijn, G.; van Belzen, M.J.; van der Grond, J.; Polke, J.M.; Bernal-Quiros, M.; Lesnik Oberstein, S.A. Archetypal NOTCH3 mutations frequent in public exome: Implications for CADASIL. Ann. Clin. Transl. Neurol. 2016, 3, 844–853. [Google Scholar] [CrossRef] [Scilit]
- Rutten, J.W.; Van Eijsden, B.J.; Duering, M.; Jouvent, E.; Opherk, C.; Pantoni, L.; Federico, A.; Dichgans, M.; Markus, H.S.; Chabriat, H.; et al. The effect of NOTCH3 pathogenic variant position on CADASIL disease severity: NOTCH3 EGFr 1-6 pathogenic variant are associated with a more severe phenotype and lower survival compared with EGFr 7-34 pathogenic variant. Genet. Med. 2019, 21, 676–682. [Google Scholar] [CrossRef] [Scilit]
- Hack, R.J.; Rutten, J.W.; Person, T.N.; Li, J.; Khan, A.; Griessenauer, C.J.; Regeneron Genetics, C.; Abedi, V.; Lesnik Oberstein, S.A.J.; Zand, R. Cysteine-Altering NOTCH3 Variants Are a Risk Factor for Stroke in the Elderly Population. Stroke 2020, 51, 3562–3569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rutten, J.W.; Hack, R.J.; Duering, M.; Gravesteijn, G.; Dauwerse, J.G.; Overzier, M.; van den Akker, E.B.; Slagboom, E.; Holstege, H.; Nho, K.; et al. Broad phenotype of cysteine-altering NOTCH3 variants in UK Biobank: CADASIL to nonpenetrance. Neurology 2020, 95, e1835–e1843. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kalaria, R.N.; Kittner, S.J. Top-NOTCH3 Variants in the Population at Large. Stroke 2020, 51, 3482–3484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tikka, S.; Baumann, M.; Siitonen, M.; Pasanen, P.; Pöyhönen, M.; Myllykangas, L.; Viitanen, M.; Fukutake, T.; Cognat, E.; Joutel, A.; et al. CADASIL and CARASIL. Brain Pathol. 2014, 24, 525–544. [Google Scholar] [CrossRef] [Scilit]
- Yamamoto, Y.; Liao, Y.C.; Lee, Y.C.; Ihara, M.; Choi, J.C. Update on the Epidemiology, Pathogenesis, and Biomarkers of Cerebral Autosomal Dominant Arteriopathy with Subcortical Infarcts and Leukoencephalopathy. J. Clin. Neurol. 2023, 19, 12–27. [Google Scholar] [CrossRef] [Scilit]
- Yuan, L.; Chen, X.; Jankovic, J.; Deng, H. CADASIL: A NOTCH3-associated cerebral small vessel disease. J. Adv. Res. 2024, 66, 223–235. [Google Scholar] [CrossRef] [Scilit]
- Locatelli, M.; Padovani, A.; Pezzini, A. Pathophysiological Mechanisms and Potential Therapeutic Targets in Cerebral Autosomal Dominant Arteriopathy with Subcortical Infarcts and Leukoencephalopathy (CADASIL). Front. Pharmacol. 2020, 11, 321. [Google Scholar] [CrossRef] [Scilit]
- Viitanen, M.; Sundström, E.; Baumann, M.; Poyhonen, M.; Tikka, S.; Behbahani, H. Experimental studies of mitochondrial function in CADASIL vascular smooth muscle cells. Exp. Cell Res. 2013, 319, 134–143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rutten, J.W.; Haan, J.; Terwindt, G.M.; van Duinen, S.G.; Boon, E.M.J.; Lesnik Oberstein, S.A.J. Interpretation of NOTCH3 mutations in the diagnosis of CADASIL. Expert Rev. Mol. Diagn. 2014, 14, 593–603. [Google Scholar] [CrossRef] [Scilit]
- Fouillade, C.; Chabriat, H.; Riant, F.; Mine, M.; Arnoud, M.; Magy, L.; Bousser, M.G.; Tournier-Lasserve, E.; Joutel, A. Activating NOTCH3 mutation in a patient with small-vessel-disease of the Brain. Human Mutat. 2008, 29, 452. [Google Scholar] [CrossRef] [Scilit]
- Schmidt, H.; Zeginigg, M.; Wiltgen, M.; Freudenberger, P.; Petrovic, K.; Cavalieri, M.; Gider, P.; Enzinger, C.; Fornage, M.; Debette, S.; et al. Genetic variants of the NOTCH3 gene in the elderly and magnetic resonance imaging correlates of age-related cerebral small vessel disease. Brain 2011, 134, 3384–3397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abou Al-Shaar, H.; Qadi, N.; Al-Hamed, M.H.; Meyer, B.F.; Bohlega, S. Phenotypic comparison of individuals with homozygous or heterozygous mutation of NOTCH3 in a large CADASIL family. J. Neurol. Sci. 2016, 367, 239–243. [Google Scholar] [CrossRef] [Scilit]
- He, R.; Li, H.; Sun, Y.; Chen, M.; Wang, L.; Zhu, Y.; Zhang, C. Homozygous NOTCH3 p.R587C mutation in Chinese patients with CADASIL: A case report. BMC Neurol. 2020, 20, 72. [Google Scholar] [CrossRef] [Scilit]
- Ragno, M.; Pianese, L.; Morroni, M.; Cacchiò, G.; Manca, A.; Di Marzio, F.; Silvestri, S.; Miceli, C.; Scarcella, M.; Onofrj, M.; et al. “CADASIL coma” in an Italian homozygous CADASIL patient: Comparison with clinical and MRI findings in age-matched heterozygous patients with the same G528C NOTCH3 mutation. Neurol. Sci. 2013, 34, 1947–1953. [Google Scholar] [CrossRef] [Scilit]
- Soong, B.-W.; Liao, Y.-C.; Tu, P.-H.; Tsai, P.-C.; Lee, I.H.; Chung, C.-P.; Lee, Y.-C. A homozygous NOTCH3 mutation p.R544C and a heterozygous TREX1 variant p.C99MfsX3 in a family with hereditary small vessel disease of the brain. J. Chin. Med. Assoc. 2013, 76, 319–324. [Google Scholar] [CrossRef] [Scilit]
- Liem, M.K.; Lesnik Oberstein, S.A.J.; Vollebregt, M.J.; Middelkoop, H.A.M.; van der Grond, J.; Helderman-van den Enden, A.T.J.M. Homozygosity for a NOTCH3 mutation in a 65-year-old CADASIL patient with mild symptoms. J. Neurol. 2008, 255, 1978–1980. [Google Scholar] [CrossRef] [Scilit]
- Mukai, M.; Mizuta, I.; Ueda, A.; Nakashima, D.; Kushimura, Y.; Noto, Y.-i.; Ohara, T.; Itoh, K.; Ando, Y.; Mizuno, T. A Japanese CADASIL patient with homozygous NOTCH3 p.Arg544Cys mutation confirmed pathologically. J. Neurol. Sci. 2018, 394, 38–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tuominen, S.; Juvonen, V.; Amberla, K.; Jolma, T.; Rinne, J.O.; Tuisku, S.; Kurki, T.; Marttila, R.; Pöyhönen, M.; Savontaus, M.-L.; et al. Phenotype of a Homozygous CADASIL Patient in Comparison to 9 Age-Matched Heterozygous Patients With the Same R133C Notch3 Mutation. Stroke 2001, 32, 1767–1774. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vinciguerra, C.; Rufa, A.; Bianchi, S.; Sperduto, A.; De Santis, M.; Malandrini, A.; Dotti, M.T.; Federico, A. Homozygosity and severity of phenotypic presentation in a CADASIL family. Neurol. Sci. 2014, 35, 91–93. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).