


Highlights
- 1.
- IgA nephropathy is a common glomerular disease and a leading cause of progression to end-stage renal disease.
- 2.
- BAFF and APRIL induce excessive B-cell activation by binding to receptors TACI, BCMA, and BAFF-R, leading to the overproduction of galactose-deficient IgA1 (Gd-IgA1).
- 3.
- Mechanism of action of BAFF/APRIL biological agents in treating IgA nephropathy.
- 4.
- Clinical trial progress of BAFF/APRIL biological agents in treating IgA nephropathy.
Abstract
IgA nephropathy (IgAN) is the most common primary chronic glomerular disease worldwide. Its clinical features include proteinuria and complement pathway activation, which are the strongest predictors of progression to renal failure. This disease can occur at any age. Approximately 30–40% of IgAN patients progress to end-stage renal disease (ESRD) within 20–25 years after diagnosis, making it one of the major causes of ESRD. As understanding of the autoimmune development of IgA nephropathy (IgAN) grows, research shows that BAFF and APRIL promote B-cell activation by binding to the receptors TACI, BCMA, and BAFF-R. This results in the overproduction of galactose-deficient IgA1 (Gd-IgA1), which helps drive the progression of IgA nephropathy. B-cell and plasma cell-targeted therapies, such as biologics against BAFF/APRIL, can precisely and effectively improve patient symptoms. Corresponding agents have now been successfully developed and are administered via subcutaneous or intravenous injection. Clinical trials have demonstrated the significant effectiveness of this approach, especially in reducing proteinuria, stabilizing eGFR, and lowering Gd-IgA1 levels. Although current trial data for BAFF/APRIL-targeted biologics in IgA nephropathy are promising, these new treatments need ongoing clinical monitoring for long-term infection risks and potential drug resistance. This article focuses on the application of BAFF/APRIL biologics in the treatment of IgA nephropathy, addressing gaps in existing literature. While prior studies have emphasized the mechanisms of action of these drugs in IgA nephropathy, they have lacked a comprehensive summary of the current status of specific drug research and clinical progress.
1. Introduction
IgA nephropathy (IgAN), as a primary glomerular disease first proposed by Jean Berger and Hinglais in 1968, is now considered to be the most common primary glomerulonephritis worldwide and a major cause of chronic kidney disease (CKD) and renal failure [1]. According to valid statistics, the annual incidence of adult IgAN is estimated to be at least 25 cases per million population per year (pmp/year) globally, with the highest incidence in Asia accounting for 30–60% of all renal biopsies, especially in Japan and China [2,3]; and medium prevalence in Europe, 20–30% of all renal biopsies, with higher prevalence in the Nordic countries than in the Southern European countries [4].
The pathogenesis of IgAN is still not fully elucidated. Core mechanism involves the abnormal production of galactose-deficient IgA1 (Gd-IgA1) due to mucosal immune dysregulation, the formation of autoantibodies against this abnormality, the deposition of immune complexes in the renal mesangial area, complement system activation, and the resulting inflammatory response and progressive renal damage [1,5,6,7,8]; and converging mechanism will finally lead to glomerular and tubulointerstitial inflammation, renal fibrosis, and renal failure [9,10]. Clinically, IgAN commonly manifests as recurrent episodes of gross hematuria or microscopic hematuria, with the most frequent presentation being asymptomatic hematuria accompanied by varying degrees of proteinuria [11].
Current conventional therapies for IgA nephropathy mainly work through immunosuppression, anti-inflammatory effects, and hemodynamic regulation, but they do not provide disease-specific targeted treatment. However, they are often linked to serious side effects, including osteoporosis from prolonged use, infections, gastrointestinal issues, and a relatively high rate of recurrence afterward discontinuation [4]. While budesonide offers a targeted therapeutic approach for IgA nephropathy, the associated treatment costs remain substantially high [12]. In regions like Japan, tonsillectomy combined with steroid pulse therapy (TSP) is also used to remove a potential source of abnormal IgA1 production. However, this method is not yet widely recommended in international guidelines, and its long-term effectiveness remains a topic of debate [13]. Although these traditional treatment approaches can manage the condition to some degree, exploring new therapeutic methods remains essential for patients’ long-term well-being.
Recent evidence suggests pivotal role of BAFF/APRIL system in development of IgAN. Therefore, precision intervention targeting IgAN at its source represents the most prominent and novel feature of BAFF/APRIL biologics, offering an entirely new therapeutic strategy for the treatment of this disease [14]. This type of targeted therapy can precisely target the source to stop the production of pathogenic IgA1, unlike traditional treatments that only address the symptoms of IgA nephropathy. It thus provides a new treatment option for IgAN. The first biologics targeting the immunopathological mechanisms of IgAN—sepelimumab and etanercept—demonstrated significant efficacy in their respective Phase III clinical trials, namely the VISIONARY and ORIGIN studies [15,16], and BAFF/APRIL inhibitors have demonstrated stable eGFR in clinical trials; additionally, the convenient administration method greatly improves ease of dosing, which improves patients’ quality of life. Therefore, exploring the applications, mechanisms, clinical advances, and challenges of BAFF/APRIL-targeting biologics in the treatment of IgAN is important for advancing precision medicine in this disease.
2. Role of BAFF/APRIL Pathway in IgAN
2.1. BAFF/APRIL Dual Ligands Mechanism and Its Signaling Pathway
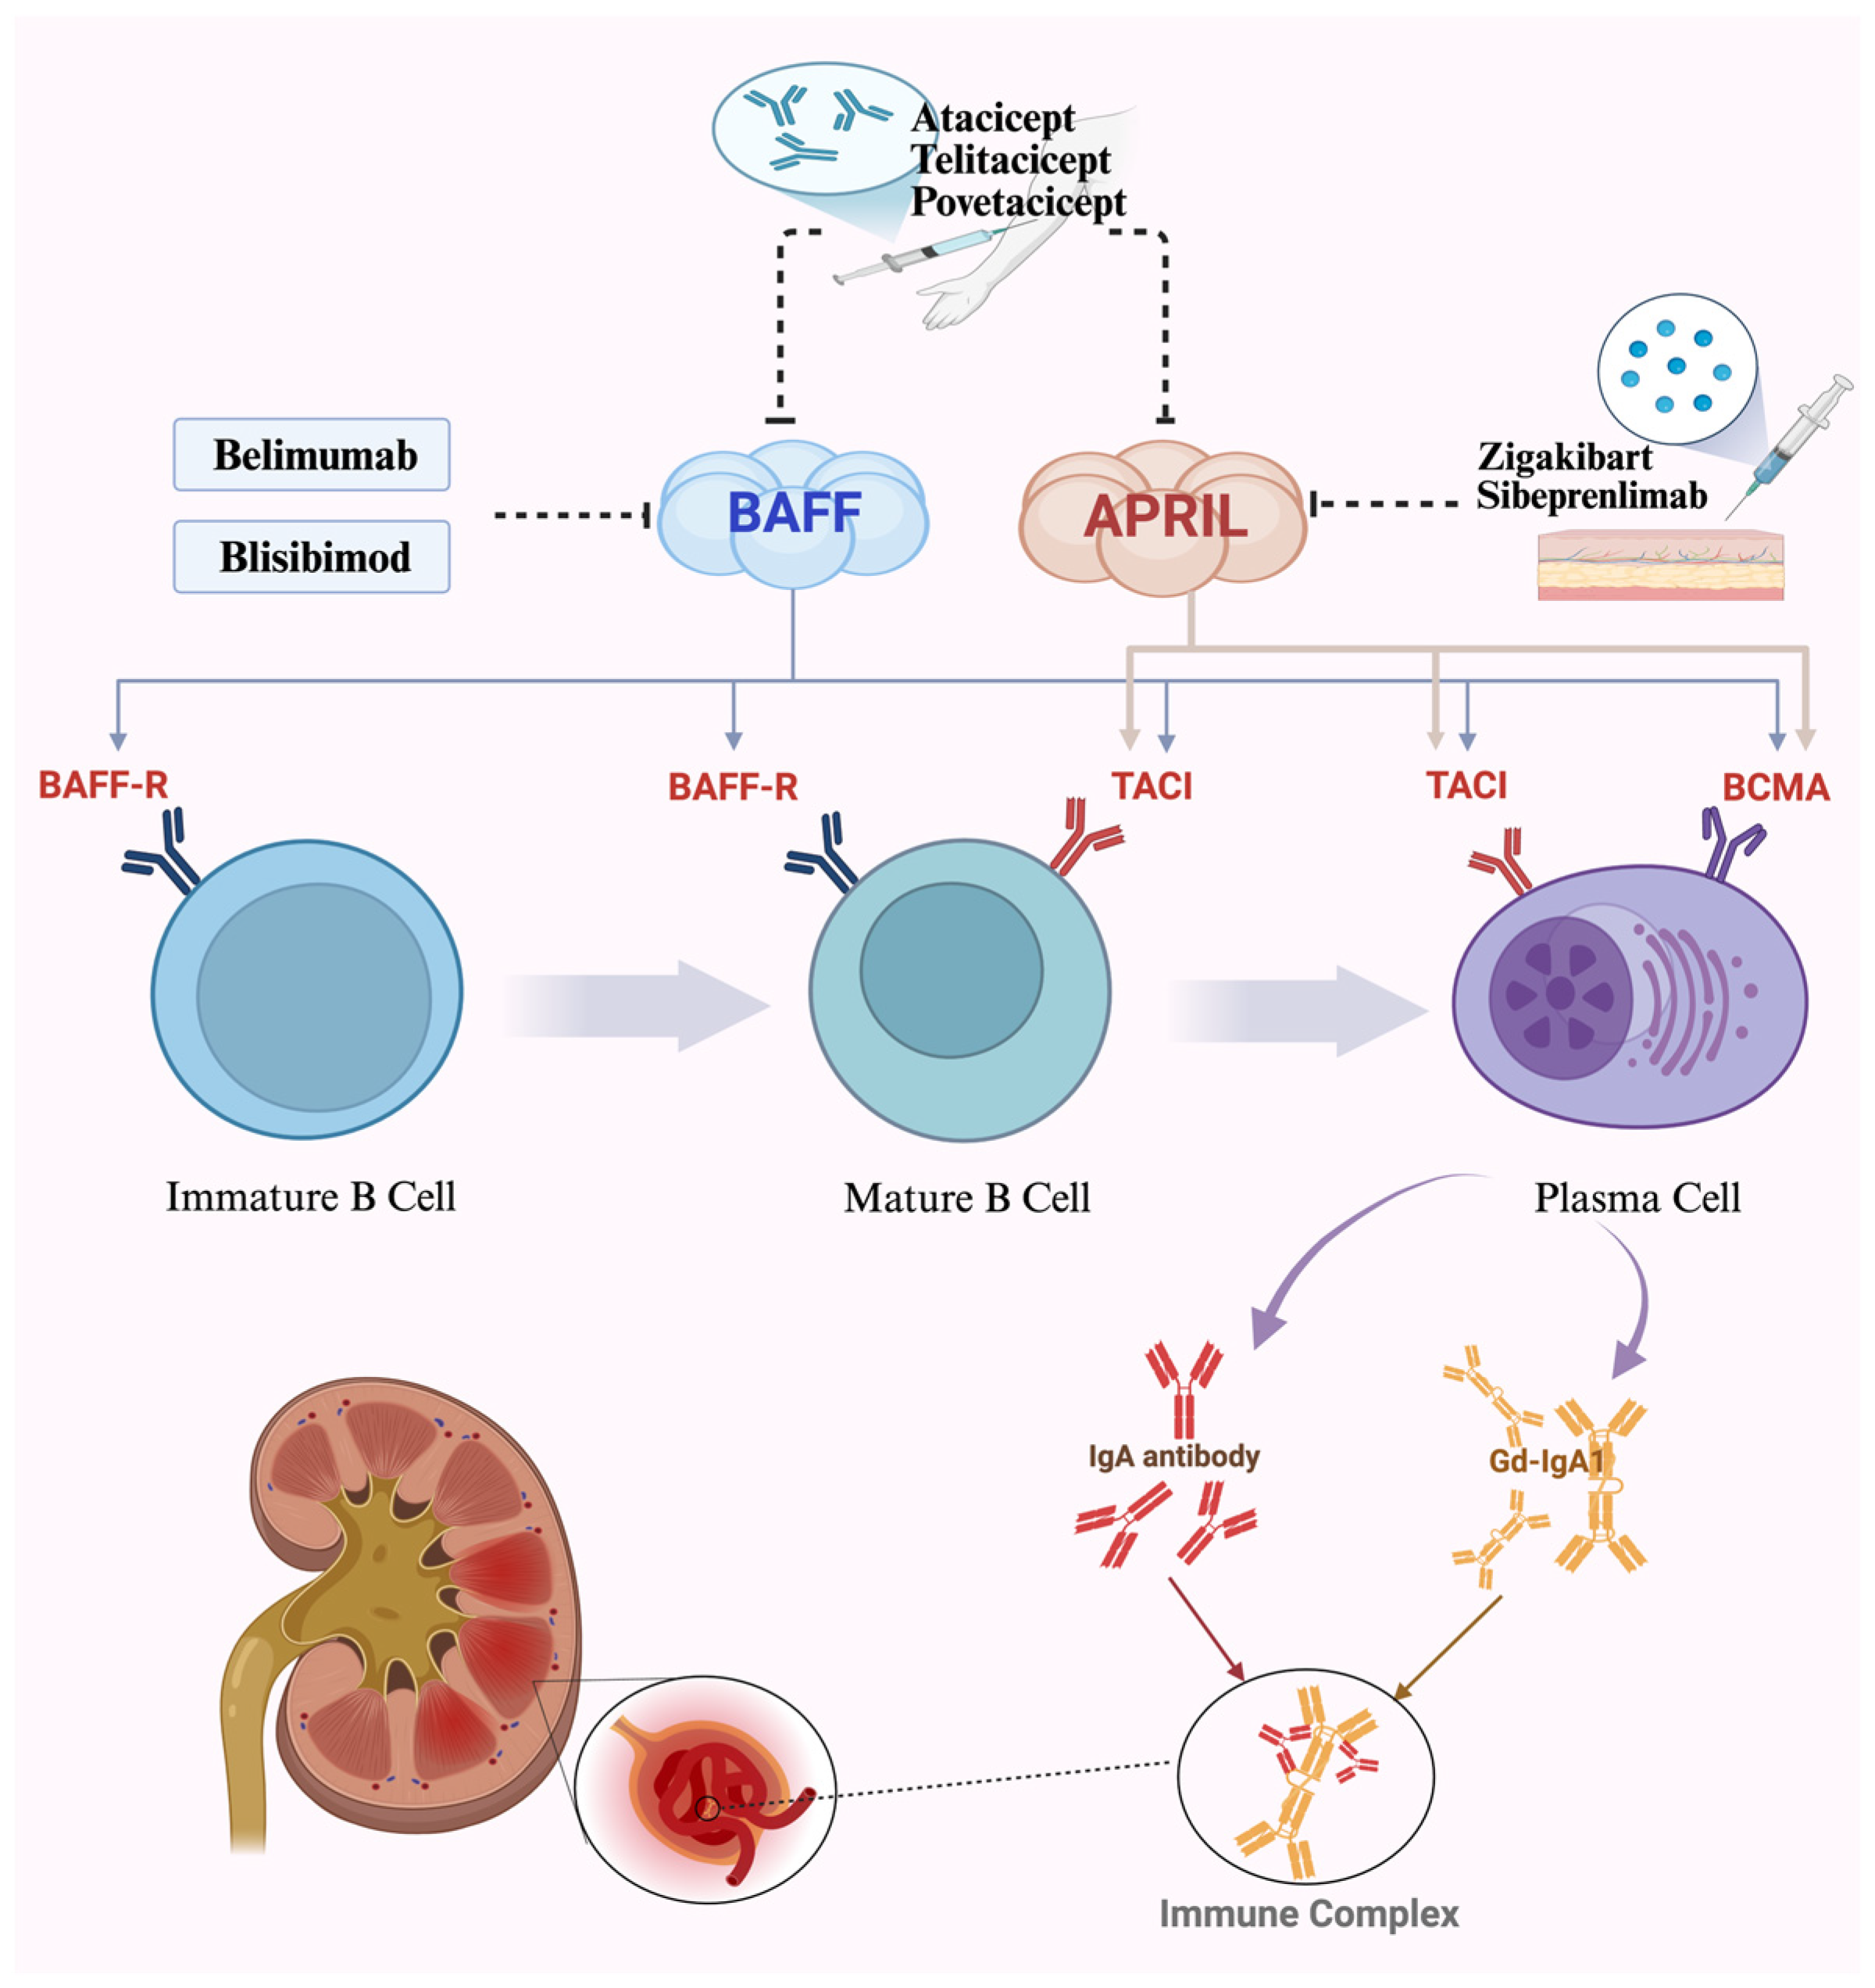
B lymphocytes activating factor (BAFF) and apical proliferation-inducing ligand (APRIL) within the tumor necrosis factor (TNF) family are structurally similar yet functionally distinct members of the TNF superfamily [17]. Although these two receptors have distinct functions, they are closely interconnected. BAFF is typically processed on the cell surface. Experimental evidence indicates that excessive BAFF production in the body can trigger severe autoimmune diseases in mice: systemic lupus erythematosus (SLE) and Sjögren’s syndrome (SS). In contrast, APRIL undergoes processing intracellularly via prohormone convertase and functions exclusively as a soluble factor, promoting proliferation in both normal and tumor cell lines [18,19]. BAFF specifically binds to BAFF receptors (BAFF-R), TACI, and BCMA, while APRIL primarily interacts with BCMA and TACI but not BAFF-R [20,21]. In autoimmune diseases, BAFF and APRIL can form heterotrimers through noncovalent interactions [22]. As crucial factors for B lymphocytes survival, maturation, and differentiation into plasma cells, they jointly regulate B lymphocytes homeostasis through interactions with receptors BAFF-R, TACI, and BCMA, exerting significant influence on T-cell-independent immune responses and immunoglobulin class switching, particularly IgA [22,23]. BAFF and APRIL form complex signaling networks through shared co-receptors TACI (Transmembrane Activator and Calcium-modulating Cyclophilin Ligand Interactor) and BCMA (B-Cell Maturation Antigen) by utilizing common signaling pathways [24,25]. Experimental evidence confirms that the two cytokines BAFF and APRIL can combine with the receptor TACI, jointly activating downstream signaling pathways (such as NF-κB) and collectively promoting B lymphocytes activation and pathogenic IgA production [26,27]. In animal models, blocking the BAFF/APRIL system (such as using the TACI-Fc fusion protein) significantly reduces kidney injury and proteinuria [22]. Additionally, BAFF activates the PI3K-Akt signaling pathway through its receptor BAFF-R, thereby participating in the regulation of T-cell activation and proliferation to exert its immunomodulatory effects [28]. It has been shown that BAFF/APRIL overexpression promotes the development of IgAN by facilitating B lymphocytes differentiation, maturation, and aberrant secretion of plasma cell antibodies (Figure 1) [29].
Figure 1.
BAFF primarily binds to BAFF-R, while APRIL mainly binds to TACI and BCMA receptors. By influencing B-cell differentiation and plasma cell survival, BAFF and APRIL induce the secretion of Igd-IgA1 (antigen) and anti-Gd-IgA1 autoantibodies, which ultimately form pathogenic immune complexes. These complexes deposit in the renal mesangial region, triggering inflammatory responses in the kidneys. Created in BioRender. Xu, Y. https://BioRender.com/2zyp2i4, accessed on 5 January 2026.
2.2. BAFF/APRIL Abnormal Activation Induces Pathogenic IgA1 Production
IgAN is an autoimmune kidney disease, and B-cells play a key role in its development and progression. B-cells differentiate into plasma cells to secrete antibodies; these antibodies bind to kidney antigens either specifically or nonspecifically, ultimately forming immune complexes that cause kidney damage [30]. Specifically, B-cells, as precursors and regulatory units, are activated upon stimulation by the receptors BAFF and APRIL, undergo class-switch recombination (CSR), and ultimately differentiate into IgA-secreting B-cells [31,32]. Subsequently, these B-cells further differentiate into effector units—plasma cells (including short-lived plasmocytes and long-lived plasma cells), with the latter migrating into the bone marrow or inflammatory tissues (such as the kidneys) [33]. A pivotal antibody secreted by these plasma cells is galactose-deficient IgA1 (Gd-IgA1). Current understanding suggests a close relationship between the production of galactose-deficient IgA1 (Gd-IgA1) and the development of IgAN [34].
BAFF/APRIL over-activation plays a central role in the production of Gd-IgA1. Studies have shown that elevated levels of BAFF and APRIL in patient serum are closely associated with disease severity indicators, such as proteinuria, decreased eGFR, and pathological damage [35,36]. Transcriptome analysis revealed widespread gene expression abnormalities in B-cells from IgAN patients, particularly in genes involved in B-cell activation and antibody production [33]. BAFF is essential for B-cell maturation and survival mainly through interaction with the BAFF receptor. Recent findings suggest that inhibiting BAFF significantly reduces the overall serum levels of IgA, IgG, and IgM. This indicates that BAFF inhibition does not specifically target IgA but instead has a broad regulatory effect on B-cell survival and differentiation, impacting multiple immunoglobulin classes. APRIL mainly influences B-cell differentiation and plasma cell survival through the TACI and BCMA receptors. These processes lead to increased production of IgA, particularly gammaglobulin-deficient IgA1. Experimental results demonstrate that APRIL is elevated in IgAN patients and correlates with disease severity [37]. In animal models, APRIL-neutralizing antibodies significantly reduce levels of abnormally glycosylated IgA, diminish glomerular IgA deposition, and improve proteinuria, indicating that APRIL specifically promotes the production of abnormally glycosylated IgA [38]. APRIL mainly helps keep mature B-cells alive, like long-lived plasma cells, which may be an important cellular source for ongoing production of abnormally glycosylated IgA. The initial B-cells are activated, differentiate into short-lived plasma cells (SLPC), and then mature into long-lived plasma cells (LLPC) within the bone marrow [39]. BAFF primarily targets mature B-cells and early plasma cells, with only limited direct support for long-lived plasma cells; APRIL is crucial for maintaining the survival of long-lived plasma cells, especially intestinal IgA+ plasma cells and bone marrow plasma cells [25]. In summary, both anti-BAFF antibodies and anti-APRIL antibodies can decrease serum IgA levels, but only anti-APRIL antibodies can block the production of abnormal antibodies and inhibit the synthesis of abnormally glycosylated IgA.
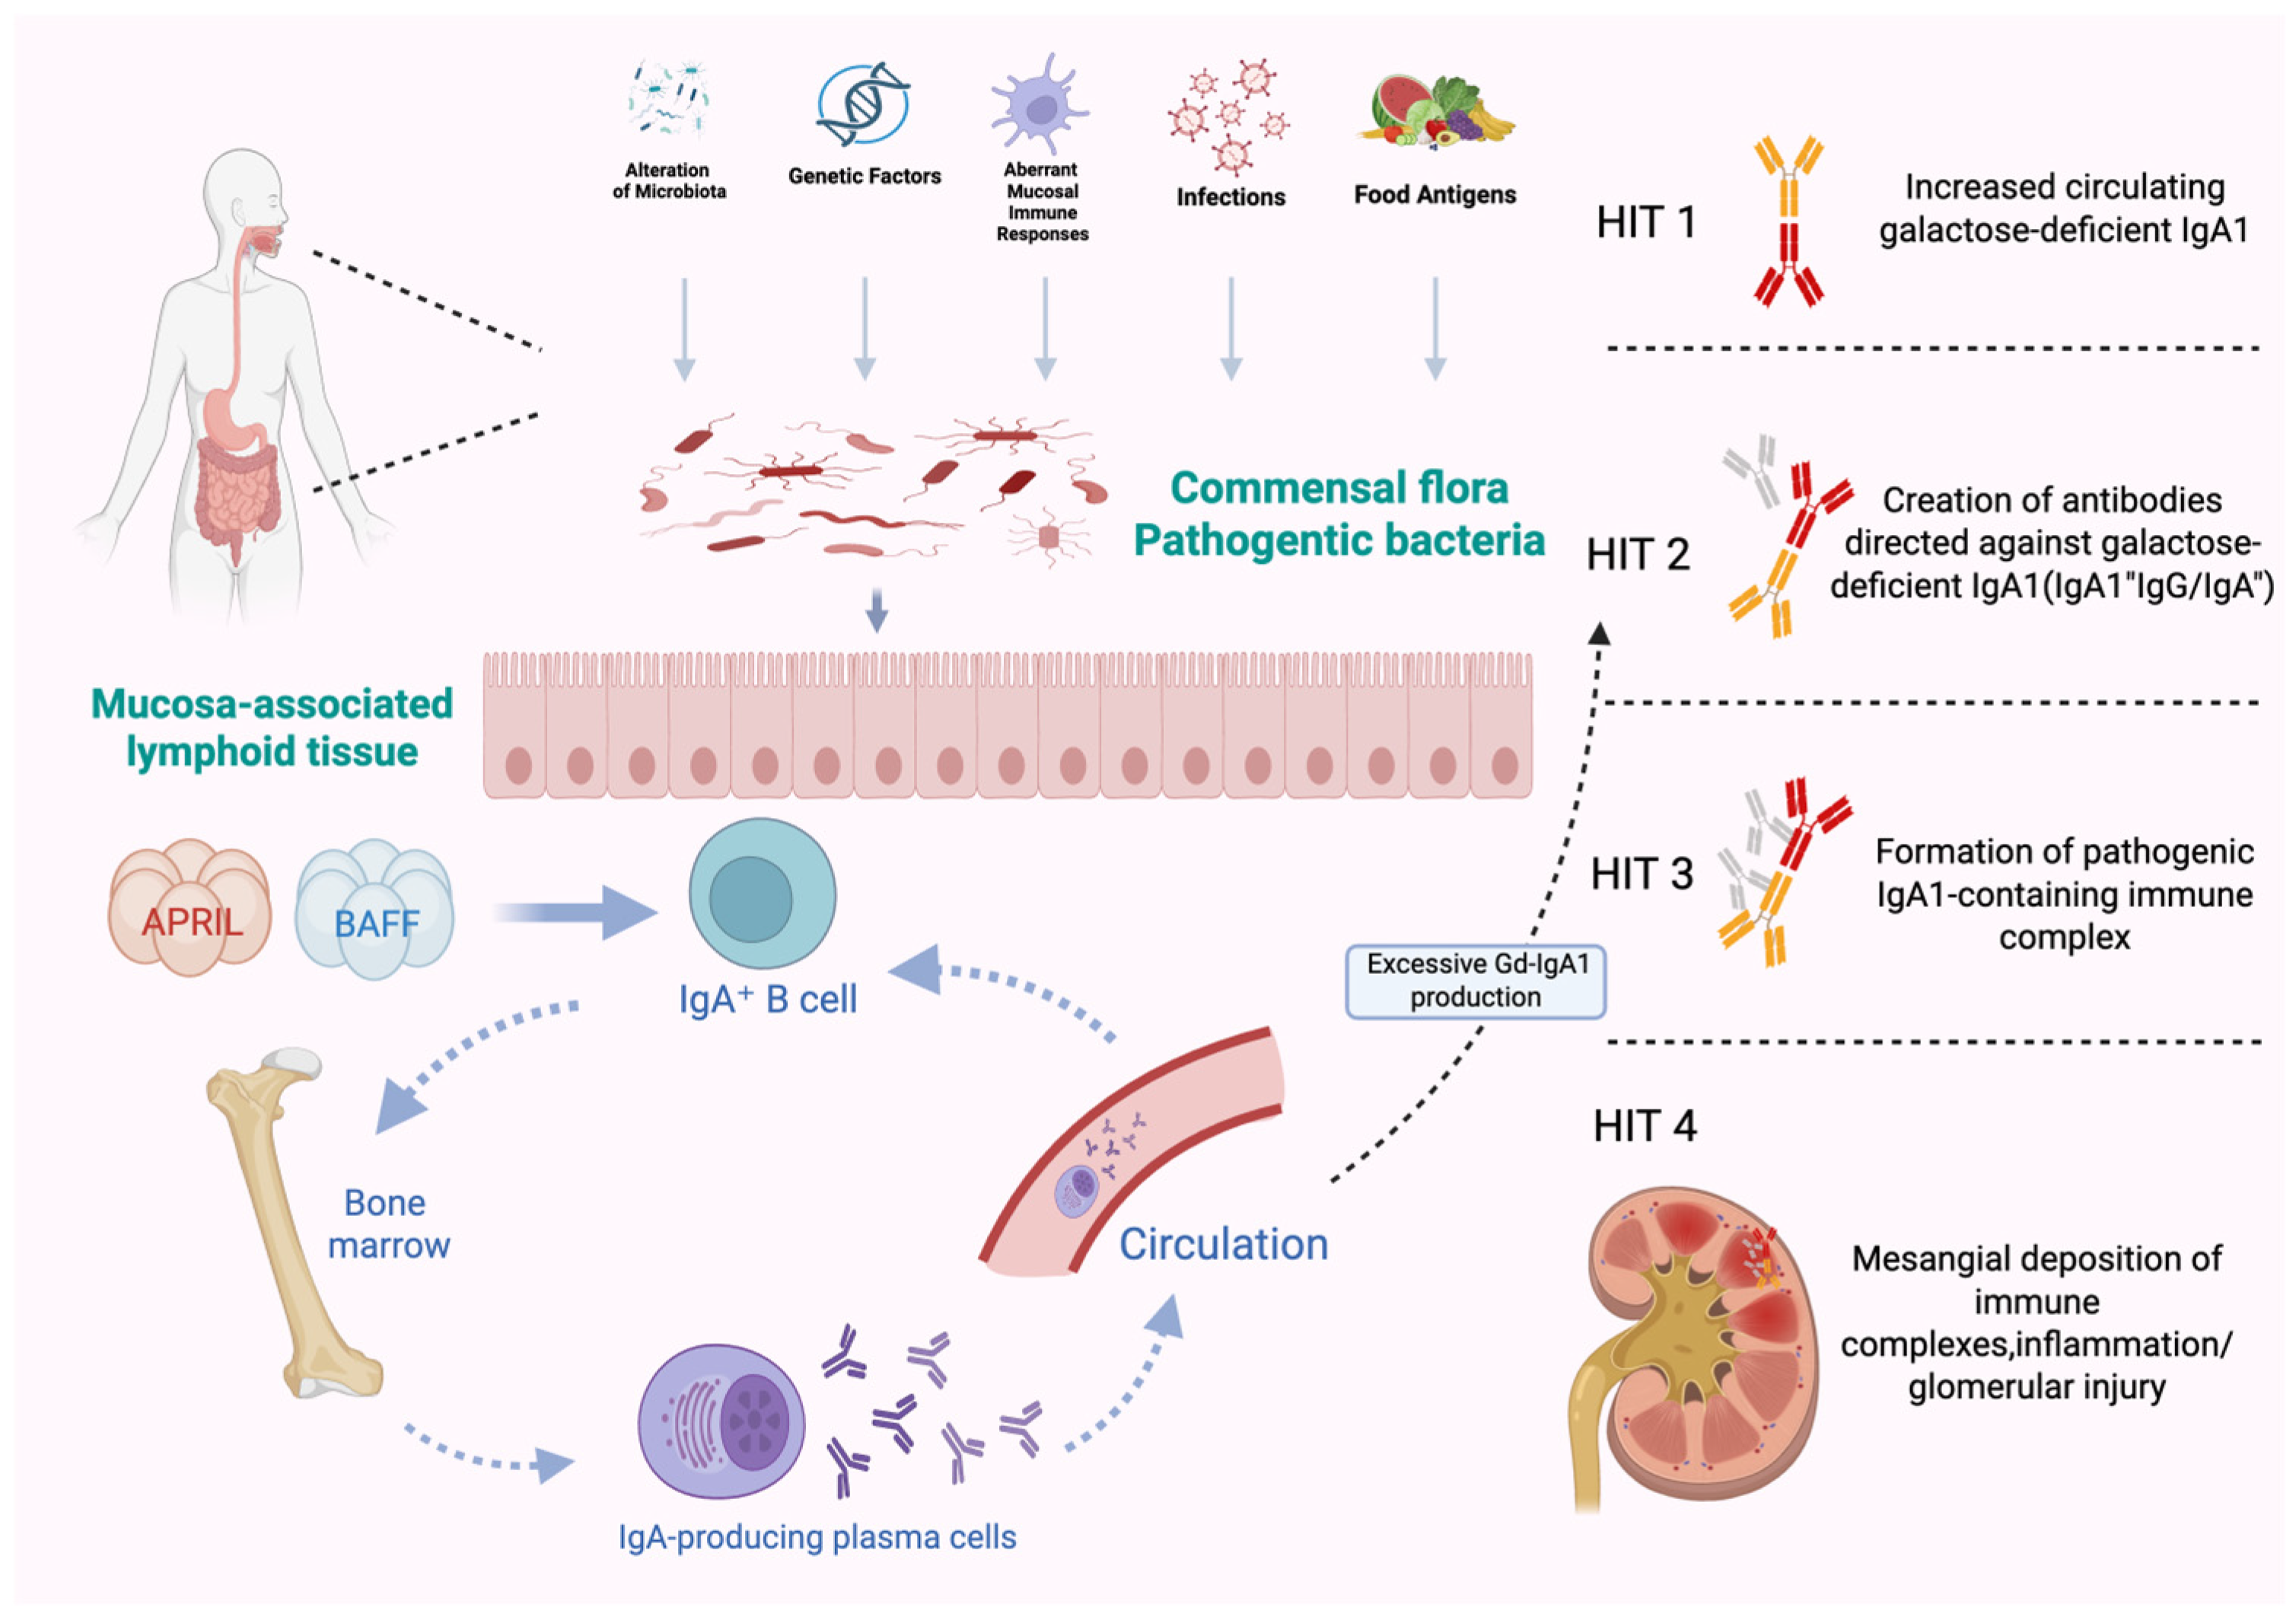
Specifically, abnormally high levels of BAFF and APRIL are associated with mucosal immune dysregulation, such as in the tonsils or gut-associated lymphoid tissue. These factors stimulate IgA1 secretion by enhancing B-cell signaling pathways (e.g., the TACI receptor-mediated pathway) and promote abnormal glycosylation patterns of Gd-IgA1 (O-glycosylation defects) by regulating the expression of key glycosyltransferases [40,41,42]. High levels of BAFF and APRIL are often connected to disruptions in mucosal immunity, particularly in the gut-associated lymphoid tissue (GALT), which plays a crucial role in the development of IgAN (Figure 2) [43]. The production of IgA+ B-cells occurs within MALT through either T-cell-dependent (TCD) or T-cell-independent (TCI) pathways. The TCD pathway is initiated by B-cell activating factor (BAFF or BLyS) and proliferin-associated receptor-activating ligand (APRIL). After forming IgA+ B-cells, they migrate through the lymphatic system and systemic circulation to mucosal effector sites under the control of homing receptors [31]. The resulting antibodies form IgA dimers composed of two IgA molecules linked by connecting chains, and are frequently detected within renal tissue [44,45].
Figure 2.
BAFF and APRIL stimulation promote B-cell differentiation and proliferation. IgA+ B-cells migrate through the lymphatic system and systemic circulation to mucosal effector sites under the regulation of homing receptors. Subsequently, they undergo hyperactivation, class switching, and differentiate into plasma cells, leading to the overproduction of galactose-deficient IgA1 (Gd-IgA1). Gd-IgA1 then forms immune complexes with autoantibodies, deposits in the glomerular mesangial region, activates the complement system, and causes inflammatory damage. Created in BioRender. Xu, Y. https://BioRender.com/39uuyhv, accessed on 16 January 2026.
In short, these two cytokines, BAFF and APRIL, drive excessive and abnormal immune complex formation by Gd-IgA1 through enhanced B-cell-mediated immune responses, ultimately leading to glomerular inflammation [46,47,48].
3. The Shift from Conventional Therapy to Precision Therapy
The current mainstream treatment for IgAN still primarily relies on glucocorticoids and broad-spectrum immunosuppressant [49]. However, these traditional treatment regimens often demonstrate notable disadvantages. The TESTING trial indicated that CS therapy for patients was associated with severe infections [50]. While other medications also posed risks of infection, gastrointestinal disturbances, and significant financial burden, thereby exacerbating patients’ physical suffering and economic strain (Table 1) [51].
In renal protection, glucocorticoids with RAS blockers suppress immune injury, while SGLT2 inhibitors delay chronic complications via metabolic regulation [52]. Tacrolimus offers renal protection by stabilizing podocytes and reducing proteinuria [53]. Etiological treatment targets mucosal immune irregularities: tonsillectomy removes abnormal immune foci, while targeted release of budesonide specifically decreases pathogenic IgA1 production [54,55]. Tacrolimus and corticosteroids also have immunomodulatory effects. Current treatment trends emphasize developing personalized regimens based on pathological subtypes, such as prioritizing immunosuppression for active lesions and focusing on metabolic regulation for chronic lesions. This approach simultaneously achieves causal intervention and renal function preservation, thereby delaying disease progression.
Calcineurin inhibitors have been studied for a long time but have not been recommended as a treatment for IgAN. Calcineurin inhibitors (CNIs) used in managing IgA nephropathy are typically classified as immunosuppressive agents, with tacrolimus and cyclosporine representing this category [56]. Previous studies have established that calcineurin inhibitors can impede the production of interleukin-2 and its receptor by restricting the dephosphorylation of activated T-cell nuclear factors. They directly suppress T-cell activity and potentially macrophage activity, while exerting an indirect inhibitory effect on B-cells [57,58]. While both BAFF and APRIL biologics focus on B-cells in treating IgA nephropathy, calcineurin inhibitors work more indirectly, only gently reducing B-cell activity instead of directly targeting them. Plus, their way of working is quite broad and does not specifically involve the BAFF/APRIL pathway.
Glucocorticoids primarily mitigate inflammatory responses within the glomeruli and renal tubulointerstitium by inhibiting the release of various inflammatory mediators, such as TNF-α and IL-6 [50]. However, they are unable to diminish the production of Gd-IgA1 [59]. RAS inhibitors primarily mitigate IgA nephropathy by decreasing proteinuria via hemodynamic mechanisms that enhance intraglomerular function pressure [60]. Sodium–Glucose Transporter 2 Inhibition (SGLT2) mainly improves hypoxia in IgA nephropathy by helping to lower glomerular capillary pressure and reduce renal oxygen consumption [61] Nefecon treatment for IgA nephropathy constitutes a significant advancement in recent years. It not only demonstrates a high affinity for glucocorticoid receptors but also specifically modulates mucosal immunity, thereby reducing pathogenic IgA1 production at its source. However, unlike BAFF/APRIL biologic therapies targeting IgA nephropathy, Nefecon demonstrates a positive effect on BAFF biomarkers, whereas its impact on APRIL biomarkers remain to be determined [62]. While it targets B-cells, it does not address IgA nephropathy through the BAFF/APRIL pathway. With the elucidation of the BAFF/APRIL pathway’s pivotal role in pathogenic IgA1 production, the advantages of BAFF/APRIL biologics in precision therapy for IgAN have become increasingly evident (Table 2) [33,63]. Abundant evidence demonstrated that this type of targeted intervention strategy not only reduces pathogenic IgA1 levels but also avoids the broad range of side effects associated with conventional treatment regimens [33,64,65].
Table 1.
Conventional strategy for IgAN.
4. BAFF/APRIL Therapy for IgAN
4.1. Single-Targeted BAFF Inhibitor
4.1.1. Belimumab
Belimumab is a recombinant human IgG-1λ monoclonal antibody that exerts its effects by specifically inhibiting B-cell activating factor (BAFF) [75]. The U.S. FDA approved belimumab for the treatment of systemic lupus erythematosus (SLE) in 2011, marking the first SLE treatment approved in nearly 60 years [76]. In a case report of a pediatric patient with refractory IgAN, the addition of belimumab to conventional therapy (such as immunosuppressive regimens) resulted in renal response and reduced proteinuria [77]. Aside from isolated clinical case reports, there are no other studies or reports on using this drug to treat IgA nephropathy.
4.1.2. Blisibimod
Blisibimod is a targeted BAFF inhibitor studied in patients with systemic lupus erythematosus. It was developed based on the success of belimumab, aiming to target both soluble and membrane-bound BAFF. Because of its high affinity, it effectively blocks all three forms of BAFF (soluble BAFF trimer, soluble 60-mer, and membrane BAFF) [78]. The Phase II/III clinical trial of Blisibimod (BRIGHT-SC; NCT02062684) was initiated in 2017 and has now concluded, although the results of the trial remain unpublished. Existing evidence suggests that the drug reduces proteinuria levels in patients with IgA nephropathy, exhibiting superior efficacy compared to placebo. However, the Phase III trial of this medication (BRILLIANT-SC; NCT02052219), which was initiated in 2015, was terminated prematurely [70].
Compared to monotherapy with BAFF antibodies, current research on BAFF/APRIL biologics for treating IgA nephropathy has shifted its focus toward both monotherapy with APRIL antibodies and dual inhibition of BAFF and APRIL antibodies.
4.2. Single-Targeted APRIL Inhibitor
4.2.1. Sibeprenlimab
It is a humanized IgG2 monoclonal antibody that specifically binds to APRIL, blocking its biological activity to reduce the production of pathogenic IgA (such as gammaglobulin deficiency-like IgA1) and decrease the deposition of IgA-related immune complexes in the kidneys, ultimately alleviating renal injury [79,80,81]. Its most distinctive feature is direct intervention at the cause of the disease, enabling precise treatment from the source rather than merely alleviating symptoms [35]. This offers a novel precision treatment approach for IgAN. A monthly subcutaneous injection is one of the advantages of Sibeprenlimab administration. Currently, Sibeprenlimab has entered Phase III clinical trials. During this phase, Sibeprenlimab has demonstrated efficacy: significantly reducing proteinuria, stabilizing renal function, and exhibiting favorable safety [80,82]. However, it remains in the mid-to-late stages of development and requires further data to support its routine clinical application.
4.2.2. Zigakibart
It is a humanized IgG4 monoclonal antibody that inhibits interactions between APRIL and its receptors BCMA and TACI, thereby reducing B-cell activation and abnormal IgA production [25,35,83]. The mode of administration for Zigakibart is a monthly subcutaneous injection. Compared to therapies requiring intravenous infusion, this treatment offers patients greater convenience and significantly improves treatment adherence. Zigakibart significantly reduces levels of free APRIL, IgA, and IgM, moderately lowers IgG levels, and most importantly, specifically reduces the production of galactosodeficiency IgA1 (Gd-IgA1), a key pathogenic factor in IgAN [84,85]. Clinical trials demonstrated that after treatment with Zigakibart, patients experienced a 60% reduction in proteinuria, with estimated glomerular filtration rate (eGFR) gradually stabilizing. All subjects exhibited good tolerability, and no serious adverse reaction was reported [85]. Phase II clinical data have confirmed the safety and efficacy of Zigakibart, with Phase III clinical trials currently underway, offering a new targeted treatment option for IgAN.
4.3. Dual Inhibitor Targeting Both BAFF and APRIL
4.3.1. Atacicept
It is an innovative TACI-Fc fusion protein whose molecular structure comprises the extracellular domain of the transmembrane activator and calmodulin-binding ligand (TACI) fused to the human IgG1 Fc segment [32,86]. Atacicept is typically administered as a once-weekly subcutaneous injection. By inhibiting the activity of these two cytokines, it reduces the production of pathogenic IgA1 and immune complex formation, thereby improving proteinuria and stabilizing renal function [37,86,87]. Double-blind studies have demonstrated that Atacicept (in both the 150 mg and 75 mg dose groups) significantly reduced the urine protein-to-creatinine ratio (UPCR) at 24 weeks of treatment, indicating its favorable therapeutic efficacy [88]. Another Phase III clinical trial (ORIGIN) confirmed the safety and pharmacodynamic value of Atacicept [16]. Atacicept shows promise as a novel targeted therapy in the treatment of IgAN.
4.3.2. Telitacicept
It is a dual-target fusion protein targeting both B-lymphocyte stimulator (BLyS) and apical protein-related inducible ligand (APRIL) [89]. Telitacicept is administered as a once-weekly dose via subcutaneous injection. Telitacicept achieves this by inhibiting the activity of these two cytokines, thereby reducing levels of Gd-IgA1 and IgA-containing immune complexes, significantly alleviating proteinuria in patients [90,91]. It can also alleviate local inflammatory responses in the glomeruli by reducing IgA deposition and the formation of immune complexes, thereby minimizing further renal damage [92,93,94]. Reports indicate that Telitacicept combined with corticosteroids and mycophenolate mofetil (MMF) demonstrated favorable safety and efficacy in the induction therapy of IgAN, effectively preserving patients’ renal function [95,96,97]; additionally, Telitacicept has demonstrated potential therapeutic value in refractory IgAN and recurrent IgAN (such as recurrence after kidney transplantation) [98]. Currently, Telitacicept has demonstrated promising therapeutic potential not only in multiple clinical studies for IgAN but also in clinical trials for other autoimmune diseases, such as systemic lupus erythematosus (SLE) and multiple sclerosis (MS) [99,100]. Telitacicept was approved in China in 2021 for the treatment of systemic lupus erythematosus (SLE). In March 2024, it received approval from China’s National Medical Products Administration (NMPA) for the treatment of IgAN.
4.3.3. Povetacicept
Povetacicept is an engineered ‘TACI-Fc’ fusion protein, with the TACI-Fc variant created through directed evolution that shows improved binding to both APRIL and BAFF [101]. TACI is a B-cell surface receptor capable of concurrently binding BLyS and APRIL with high affinity. By inhibiting BAFF and APRIL, this pharmaceutical agent prevents the synthesis of pathogenic gammaglobulin deficiency-associated IgA1 (Gd-IgA1), thereby mitigating renal damage resulting from immune complex deposition and exerting a disease-modifying effect [102]. In the 2024 RUBY-3 povetacicept (NCT05732402) study phase, at 9 months (n = 6), treatment with 80 mg povetacicept resulted in a 64% reduction in urinary protein-to-creatinine ratio (UPCR) and a 69% decrease in Gd-IgA1 protein; 67% of patients achieved remission status, with all patients exhibiting hematuria at baseline experiencing resolution of this symptom. Renal function remained stable, demonstrating significant clinical efficacy [103]. In late-stage RUBY-3 trials, povetacicept (NCT05732402) showed that IgAN patients that received the 80 mg dose achieved a 64% mean reduction from baseline in 24-h urine protein-to-creatinine ratio (UPCR), and estimated glomerular filtration rate (eGFR) remained stable at week 48. Approximately 90% of patients experienced resolution of hematuria, with 53% achieving clinical remission. The 240 mg dose group demonstrated efficacy comparable to the 80 mg [104].
Based on the previous discussion, we classify the patient subgroups appropriate for APRIL inhibitor therapy into the following three groups: 1. Patients mainly rely on APRIL for plasma cell survival—APRIL primarily maintains long-lived plasma cells through the TACI and BCMA receptors, while BAFF has a weaker role in supporting these cells. 2. Patients at higher risk of infection, including children, elderly individuals, those with chronic infections (such as recurrent respiratory or gastrointestinal infections), or those with immunocompromised conditions, may be prioritized for APRIL selective inhibitors to maintain some BAFF-mediated immune defense functions. 3. Patients aiming to minimize the impact of treatment on the overall immune system and focus intervention solely on the pathogenic IgA1 pathway—APRIL specifically promotes the production of abnormally glycosylated IgA1, while BAFF exerts regulatory effects across multiple immunoglobulin classes.
Monotherapy with anti-APRIL may be sufficiently effective for most IgAN patients, although dual BAFF/APRIL blockade offers greater mechanistic potential, especially for patient groups whose plasma cell survival relies on dual BAFF/APRIL signaling. Future studies should further examine the long-term efficacy and safety of these two treatment options.
Table 2.
BAFF/APRIL Biological Agents for the Treatment of IgA Nephropathy.
5. Current Challenges and Future Directions
5.1. Long-Term Safety Monitoring Requirements (Infection Risk and Immune Surveillance)
Since BAFF and APRIL are key regulators of B-cell differentiation, survival, and antibody production, BAFF/APRIL inhibitors (such as sibeprenlimab and atacicept) target these B-cell activation factors to suppress plasma cell survival and antibody production, thereby achieving therapeutic effects in IgAN [25,108,109]. However, the most direct risk of long-term suppression of B-cell function is a decline in the body’s ability to defend against pathogens, particularly extracellular bacteria and viruses [41]. Additionally, BAFF/APRIL participates in intestinal IgA class switching, so inhibiting BAFF/APRIL may also compromise the intestinal immune barrier function. Long-term use requires monitoring for respiratory or intestinal infections associated with mucosal immunity [110]. Additionally, since the function of B-cells and T-cells harboring virus-specific memory may be disrupted by BAFF/APRIL inhibitors, there is a risk of reactivation of latent varicella-zoster virus in the body [111,112,113]. Therefore, monitoring skin pain, itching, or herpes manifestations is crucial in the treatment of IgAN. Inhibition of BAFF/APRIL may lead to decreased levels of non-IgA immunoglobulins (such as IgG and IgM), so hypo-gammaglobulinemia and the associated risk of infection should also be included in monitoring parameters [114]. In response to the aforementioned risks, ongoing clinical trials of BAFF/APRIL biological inhibitors should be expedited to Phase III while simultaneously extending patient follow-up periods to promptly evaluate delayed adverse events [70]. It is recommended to incorporate BAFF/APRIL levels, Gd-IgA1 titers, and complement activation markers to correlate their efficacy and safety [35,115]. Finally, individualized monitoring plans should be developed for children, the elderly, or patients with chronic infections to ensure medication safety [116,117].
5.2. Mechanisms of Drug Resistance and Second Treatment Options
To date, no specific molecular mechanisms underlying its drug resistance have been explicitly reported in the existing literature. However, based on relevant studies, the following four aspects can be summarized:
(1) Activation of the TRAF6/NF-κB signaling pathway promotes the expression of fibrotic factors in glomerular mesangial cells, whereas the BAFF-R Fc chimeric protein inhibits this pathway [118,119]. If compensatory activation of alternative signaling pathways (such as other TNF family members) occurs, resistance may develop.
(2) BAFF/APRIL functional redundancy: BAFF and APRIL exhibit partially overlapping functions in B-cell activation and IgA production [108,120]. Therefore, in the treatment of IgAN, inhibiting a single molecule may lead to compensatory upregulation of BAFF.
(3) Receptor competition and heterogeneity: BAFF and APRIL share the receptor TACI, but BAFF can also exert effects through BAFF-R [48,83,121]. So when using only APRIL inhibitors to treat IgAN, therapeutic efficacy might be limited by the failure to sequester BAFF-R-mediated signals [122].
(4) Gut-kidney axis escape: BAFF/APRIL produced locally in tissues, such as the intestine, may not be affected by systemic inhibition, thereby leading to drug resistance [65,123,124].
To prevent the development of the aforementioned drug resistance, we can promptly adjust the treatment regimen when using BAFF/APRIL therapy for IgAN to achieve optimal therapeutic outcomes. In treatment, dual-target inhibitors or combination therapy with anti-BAFF/APRIL antibodies may represent a more comprehensive strategy [125,126]. Targeting downstream signaling molecules should not be overlooked; inhibiting the TRAF6/NF-κB pathway may enhance therapeutic efficacy [127,128]. Additionally, it can be used in combination with growth hormone inhibitors to enhance resistance [70]. Finally, to address escape via the gut-kidney axis, active modulation of gut immunity can reduce the intestinal sources of BAFF/APRIL [129,130].
6. Discussion
The TESTING trial (The Efficacy of Steroids in IgA Nephropathy Globally) was conducted among Chinese participants with a high disease prevalence. The trial was prematurely halted in the oral, high-dose, daily methylprednisolone group due to a high number of serious adverse events. After restarting the trial, administering a lower steroid dose on alternate days, combined with increased prophylaxis against pneumocystis pneumonia, has reduced infection rates [50]. A rapid decline in proteinuria indicates effective control of glomerular inflammation and immune complex deposition. Multiple studies, such as the TESTING trial, show that decreased proteinuria is associated with a slower decline in renal function, making it a primary endpoint in clinical trials recognized by both the FDA (Food and Drug Administration) and the EMA (European Medicines Agency). The significance of the eGFR slope as a long-term outcome measure lies in its role as a direct indicator of kidney function decline. The eGFR slope reflects long-term changes in glomerular filtration rate and serves as a key predictor of whether the disease has progressed to end-stage renal disease (ESRD). Although a reduction in proteinuria may suggest stable eGFR, some patients may experience a “proteinuria-eGFR disconnect,” where glomerular function (eGFR) appears normal despite significant protein leakage in the urine (proteinuria). Therefore, the eGFR slope is a vital marker for confirming whether treatment effectively preserves renal function. Nevertheless, a comprehensive assessment of long-term renal protection should also include histological improvements and biomarkers, such as Gd-IgA1 levels. In the short term, focus should be on monitoring the reduction in proteinuria, as this serves as an early indicator of treatment effectiveness. However, long-term management requires ongoing assessment of the eGFR slope to ensure that treatment not only relieves symptoms but also significantly slows the progression of IgA nephropathy.
Based on currently limited evidence, we cautiously conclude that new biologic treatments targeting BAFF/APRIL may reduce the 24-h urine protein-to-creatinine ratio (UPCR) and circulating Gd-IgA1 levels in patients with IgAN, while potentially slowing the decline in estimated glomerular filtration rate (eGFR). It is noteworthy that BAFF/APRIL dual antagonists might lower serum levels of IgG, IgA, and IgM, potentially impairing patients’ immune defenses. New biologic treatments targeting BAFF/APRIL are in Phase III trials. We must continue monitoring their safety to confirm they are safe and effective.
Regarding the placement of BAFF/APRIL-targeted therapies in current clinical practice, we believe that, before approval of Phase III data, they may be used as a priority option in clinical trials or off-label (based on Phase II evidence) for high-risk patients who have failed standard treatment. If Phase III data prove favorable, this could become a novel therapeutic option for high-risk progressive IgA nephropathy, especially for patients intolerant to corticosteroids or seeking safer targeted therapies. However, its final positioning will depend on evidence of long-term kidney protection, safety data, pricing, and healthcare reimbursement policies. If successful, this could transform the treatment approach for IgA nephropathy, marking an important shift from supportive care to targeted immunomodulation.
7. Conclusions
Based on current research progress, BAFF/APRIL biologics demonstrate breakthrough potential in the treatment of IgAN; however, larger-scale clinical trials and laboratory studies are still needed to demonstrate the long-term efficacy and safety of BAFF/APRIL biologics in the treatment of IgAN. Despite these challenges, targeted intervention in the BAFF/APRIL system holds promise to reshape the therapeutic landscape for IgAN, particularly for patients unresponsive to conventional treatments [14,131]. In recent years, the discovery of several new biomarkers has opened up new possibilities for personalized medicine in IgAN. These include Gd-IgA1 and its antibodies, components of the complement system (such as C4d and FHR-1), urinary protein markers (such as MMP-7 and KIM-1), and microRNAs (such as miR-148b and let-7b), which show promise for both diagnosis and prognosis assessment [132,133]. Therefore, the future management of IgA nephropathy could benefit from enhanced comprehensive assessment of multidimensional biomarkers. This includes developing a risk stratification model that integrates clinical indicators (e.g., proteinuria, eGFR), pathological scores (MEST-C), and molecular biomarkers (e.g., Gd-IgA1, miRNA, complement). Additionally, it is important to develop therapeutic response and prognostic assessments tailored to different treatments (e.g., corticosteroids, targeted therapies). Standardizing detection methods and broadening sample diversity can promote the clinical translation and universal validation of biomarkers, ultimately shifting from a one-size-fits-all approach to precision, stratified diagnostic and therapeutic strategies.
8. Literature Search
This manuscript is a non-systematic narrative review. This study mainly conducted searches in the PubMed database, Google Scholar, and ClinicalTrials.gov. The references include publications from 2002 to 2025, with more focus on those published between 2015 and 2025.
Funding
This research was funded by Science and Technology Development Fund of Macau grant number [File Nos. 0022/2024/RIB1 and 0104/2024/AGJ] and the APC was funded by [Science and Technology Development Fund of Macau].
Data Availability Statement
No new data were created or analyzed in this study.
Acknowledgments
During the preparation of this manuscript/study, the author(s) used BioRender for the purposes of Image rendering. The authors have reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Shimizu, Y.; Tomino, Y.; Suzuki, Y. IgA Nephropathy: Beyond the Half-Century. Medicina 2023, 60, 54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, Y.; Xu, B.; Shi, S.; Zhou, X.; Chen, P.; Liu, L.; Li, Y.; Leng, Y.; Lv, J.; Zhu, L.; et al. Mesangial C3 Deposition, Complement-Associated Variant, and Disease Progression in IgA Nephropathy. Clin. J. Am. Soc. Nephrol. 2023, 18, 1583–1591. [Google Scholar] [CrossRef] [Scilit]
- Lee, M.; Suzuki, H.; Nihei, Y.; Matsuzaki, K.; Suzuki, Y. Ethnicity and IgA nephropathy: Worldwide differences in epidemiology, timing of diagnosis, clinical manifestations, management and prognosis. Clin. Kidney J. 2023, 16, ii1–ii8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, H.; Barratt, J. Is IgA nephropathy the same disease in different parts of the world? Semin. Immunopathol. 2021, 43, 707–715. [Google Scholar] [CrossRef] [Scilit]
- Donadio, J.V.; Grande, J.P. IgA nephropathy. N. Engl. J. Med. 2002, 347, 738–748. [Google Scholar] [CrossRef] [Scilit]
- Lai, K.N.; Tang, S.C.; Schena, F.P.; Novak, J.; Tomino, Y.; Fogo, A.B.; Glassock, R.J. IgA nephropathy. Nat. Rev. Dis. Primers 2016, 2, 16001. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Feng, Y.; Li, M.; Yang, M.; Shi, G.; Xuan, Z.; Yin, D.; Xu, F. Traditional Chinese Medicine in the Treatment of Chronic Kidney Diseases: Theories, Applications, and Mechanisms. Front. Pharmacol. 2022, 13, 917975. [Google Scholar] [CrossRef] [Scilit]
- Roberts, L.; Jones, M.; Barratt, J.; Selvaskandan, H. IgA nephropathy: A paradigm shift in treatment strategies. Curr. Opin. Nephrol. Hypertens. 2025, 34, 381–388. [Google Scholar] [CrossRef] [Scilit]
- Appel, G.B.; Waldman, M. The IgA nephropathy treatment dilemma. Kidney Int. 2006, 69, 1939–1944. [Google Scholar] [CrossRef] [Scilit]
- Barratt, J.; Barbour, S.J.; Brenner, R.M.; Cooper, K.; Wei, X.; Eren, N.; Floege, J.; Jha, V.; Kim, S.G.; Maes, B.; et al. Long-Term Results from an Open-Label Extension Study of Atacicept for the Treatment of IgA Nephropathy. J. Am. Soc. Nephrol. 2025, 36, 679–687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zand, L.; Fervenza, F.C.; Coppo, R. Microscopic hematuria as a risk factor for IgAN progression: Considering this biomarker in selecting and monitoring patients. Clin. Kidney J. 2023, 16, ii19–ii27. [Google Scholar] [CrossRef] [Scilit]
- El Karoui, K.; Fervenza, F.C.; De Vriese, A.S. Treatment of IgA Nephropathy: A Rapidly Evolving Field. J. Am. Soc. Nephrol. 2024, 35, 103–116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moriyama, T.; Nitta, K. Tonsillectomy and steroid pulse therapy for IgA nephropathy. Tohoku J. Exp. Med. 2011, 224, 243–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, J.; Xing, J.; Zhang, Y.; Liu, G. Efficacy and safety of biologic agents for IgA nephropathy: A protocol for systematic review and meta-analysis. PLoS ONE 2024, 19, e0298732. [Google Scholar] [CrossRef] [Scilit]
- Perkovic, V.; Trimarchi, H.; Tesar, V.; Lafayette, R.; Wong, M.G.; Barratt, J.; Suzuki, Y.; Liew, A.; Zhang, H.; Carroll, K.; et al. Sibeprenlimab in IgA Nephropathy—Interim Analysis of a Phase 3 Trial. N. Engl. J. Med. 2025. [Google Scholar] [CrossRef] [Scilit]
- Lafayette, R.; Barbour, S.J.; Brenner, R.M.; Campbell, K.N.; Doan, T.; Eren, N.; Floege, J.; Jha, V.; Kim, B.S.; Liew, A.; et al. A Phase 3 Trial of Atacicept in Patients with IgA Nephropathy. N. Engl. J. Med. 2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mackay, F.; Ambrose, C. The TNF family members BAFF and APRIL: The growing complexity. Cytokine Growth Factor Rev. 2003, 14, 311–324. [Google Scholar] [CrossRef] [Scilit]
- Mackay, F.; Schneider, P.; Rennert, P.; Browning, J. BAFF AND APRIL: A tutorial on B cell survival. Annu. Rev. Immunol. 2003, 21, 231–264. [Google Scholar] [CrossRef] [Scilit]
- Daridon, C.; Youinou, P.; Pers, J.O. BAFF, APRIL, TWE-PRIL: Who’s who? Autoimmun. Rev. 2008, 7, 267–271. [Google Scholar] [CrossRef] [Scilit]
- Das, S.; Sutoh, Y.; Cancro, M.P.; Rast, J.P.; Han, Q.; Bommakanti, G.; Cooper, M.D.; Hirano, M. Ancient BCMA-like Genes Herald B Cell Regulation in Lampreys. J. Immunol. 2019, 203, 2909–2916. [Google Scholar] [CrossRef] [Scilit]
- Martin, J.; Cheng, Q.; Laurent, S.A.; Thaler, F.S.; Beenken, A.E.; Meinl, E.; Krönke, G.; Hiepe, F.; Alexander, T. B-Cell Maturation Antigen (BCMA) as a Biomarker and Potential Treatment Target in Systemic Lupus Erythematosus. Int. J. Mol. Sci. 2024, 25, 10845. [Google Scholar] [CrossRef] [Scilit]
- Vincent, F.B.; Saulep-Easton, D.; Figgett, W.A.; Fairfax, K.A.; Mackay, F. The BAFF/APRIL system: Emerging functions beyond B cell biology and autoimmunity. Cytokine Growth Factor Rev. 2013, 24, 203–215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mackay, F.; Schneider, P. Cracking the BAFF code. Nat. Rev. Immunol. 2009, 9, 491–502. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Y.M.; Shaw, K.; Zhang, G.Y.; Chung, E.Y.M.; Hu, M.; Cao, Q.; Wang, Y.; Zheng, G.; Wu, H.; Chadban, S.J.; et al. Interleukin-33 Exacerbates IgA Glomerulonephritis in Transgenic Mice Overexpressing B Cell Activating Factor. J. Am. Soc. Nephrol. 2022, 33, 966–984. [Google Scholar] [CrossRef] [Scilit]
- Eslami, M.; Schuepbach-Mallepell, S.; Diana, D.; Willen, L.; Kowalczyk-Quintas, C.; Desponds, C.; Peter, B.; Vigolo, M.; Renevey, F.; Donzé, O.; et al. Unique and redundant roles of mouse BCMA, TACI, BAFF, APRIL, and IL-6 in supporting antibody-producing cells in different tissues. Proc. Natl. Acad. Sci. USA 2024, 121, e2404309121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aguirre-Valencia, D.; Ríos-Serna, L.J.; Posso-Osorio, I.; Naranjo-Escobar, J.; López, D.; Bedoya-Joaqui, V.; Nieto-Aristizábal, I.; Castro, A.M.; Díaz-Ordoñez, L.; Navarro, E.P.; et al. Expression of BAFF, APRIL, and cognate receptor genes in lupus nephritis and potential use as urinary biomarkers. J. Transl. Autoimmun. 2020, 3, 100027. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Zhao, Y.; Sun, W.; Zhang, C.; Yu, Y.; Du, B.; Jin, A.; Liu, Y. Neutrophil depletion attenuates antibody-mediated rejection in a renal transplantation mouse model. Clin. Exp. Immunol. 2024, 216, 211–219. [Google Scholar] [CrossRef] [Scilit]
- Hu, S.; Wang, R.; Zhang, M.; Liu, K.; Tao, J.; Tai, Y.; Zhou, W.; Wang, Q.; Wei, W. BAFF promotes T cell activation through the BAFF-BAFF-R-PI3K-Akt signaling pathway. Biomed. Pharmacother. 2019, 114, 108796. [Google Scholar] [CrossRef] [Scilit]
- Currie, E.G.; Coburn, B.; Porfilio, E.A.; Lam, P.; Rojas, O.L.; Novak, J.; Yang, S.; Chowdhury, R.B.; Ward, L.A.; Wang, P.W.; et al. Immunoglobulin A nephropathy is characterized by anticommensal humoral immune responses. JCI Insight 2022, 7, e141289. [Google Scholar] [CrossRef] [Scilit]
- Schrezenmeier, E.; Jayne, D.; Dörner, T. Targeting B Cells and Plasma Cells in Glomerular Diseases: Translational Perspectives. J. Am. Soc. Nephrol. 2018, 29, 741–758. [Google Scholar] [CrossRef] [Scilit]
- Cheung, C.K.; Suzuki, Y. How should we target and reduce the production of pathogenic IgA in IgAN? Nephrol. Dial. Transplant. 2025, gfaf185. [Google Scholar] [CrossRef] [Scilit]
- Cheung, C.K.; Barratt, J.; Liew, A.; Zhang, H.; Tesar, V.; Lafayette, R. The role of BAFF and APRIL in IgA nephropathy: Pathogenic mechanisms and targeted therapies. Front. Nephrol. 2023, 3, 1346769. [Google Scholar] [CrossRef] [Scilit]
- Gan, Y.; Li, J.; Li, W.; Han, Q.; Zhang, R.; Yu, H.; Zeng, W.; Qing, F.; Luo, M.; Li, H.; et al. Dynamics of chromatin accessibility governing Gd-IgA1 synthesis in B cells associated with IgA nephropathy. Exp. Mol. Med. 2025, 57, 1593–1606. [Google Scholar] [CrossRef] [Scilit]
- Lai, K.N. Pathogenesis of IgA nephropathy. Nat. Rev. Nephrol. 2012, 8, 275–283. [Google Scholar] [CrossRef] [Scilit]
- Yeo, S.C.; Barratt, J. The contribution of a proliferation-inducing ligand (APRIL) and other TNF superfamily members in pathogenesis and progression of IgA nephropathy. Clin. Kidney J. 2023, 16, ii9–ii18. [Google Scholar] [CrossRef] [Scilit]
- Xin, G.; Shi, W.; Xu, L.X.; Su, Y.; Yan, L.J.; Li, K.S. Serum BAFF is elevated in patients with IgA nephropathy and associated with clinical and histopathological features. J. Nephrol. 2013, 26, 683–690. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, Y.L.; Zhu, L.; Shi, S.F.; Liu, L.J.; Lv, J.C.; Zhang, H. Increased APRIL Expression Induces IgA1 Aberrant Glycosylation in IgA Nephropathy. Medicine 2016, 95, e3099. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Myette, J.R.; Kano, T.; Suzuki, H.; Sloan, S.E.; Szretter, K.J.; Ramakrishnan, B.; Adari, H.; Deotale, K.D.; Engler, F.; Shriver, Z.; et al. A Proliferation Inducing Ligand (APRIL) targeted antibody is a safe and effective treatment of murine IgA nephropathy. Kidney Int. 2019, 96, 104–116. [Google Scholar] [CrossRef] [Scilit]
- Funakoshi, K.; Koike, T.; Ise, W.; Tai, Y.; Narazaki, M.; Kumanogoh, A.; Inoue, T.; Kurosaki, T. TACI is required for the survival of short- and long-lived plasma cells. Int. Immunol. 2025, dxaf067. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, Y.X.; He, L.Y.; Chen, X.; Peng, X.F.; Ye, M.Y.; Zhao, Y.J.; Yan, W.Z.; Liu, C.; Shao, J.; Peng, Y.M. Potential diagnostic biomarkers for IgA nephropathy: A comparative study pre- and post-tonsillectomy. Int. Urol. Nephrol. 2016, 48, 1855–1861. [Google Scholar] [CrossRef] [Scilit]
- Takahara, M.; Nagato, T.; Nozaki, Y.; Kumai, T.; Katada, A.; Hayashi, T.; Harabuchi, Y. A proliferation-inducing ligand (APRIL) induced hyper-production of IgA from tonsillar mononuclear cells in patients with IgA nephropathy. Cell. Immunol. 2019, 341, 103925. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamada, K.; Huang, Z.Q.; Reily, C.; Green, T.J.; Suzuki, H.; Novak, J.; Suzuki, Y. LIF/JAK2/STAT1 Signaling Enhances Production of Galactose-Deficient IgA1 by IgA1-Producing Cell Lines Derived from Tonsils of Patients with IgA Nephropathy. Kidney Int. Rep. 2024, 9, 423–435. [Google Scholar] [CrossRef] [Scilit]
- Gesualdo, L.; Di Leo, V.; Coppo, R. The mucosal immune system and IgA nephropathy. Semin. Immunopathol. 2021, 43, 657–668. [Google Scholar] [CrossRef] [Scilit]
- Gutzeit, C.; Magri, G.; Cerutti, A. Intestinal IgA production and its role in host-microbe interaction. Immunol. Rev. 2014, 260, 76–85. [Google Scholar] [CrossRef] [Scilit]
- Luvizotto, M.J.; Menezes-Silva, L.; Woronik, V.; Monteiro, R.C.; Câmara, N.O.S. Gut-kidney axis in IgA nephropathy: Role on mesangial cell metabolism and inflammation. Front. Cell Dev. Biol. 2022, 10, 993716. [Google Scholar] [CrossRef] [Scilit]
- Jackson, S.W.; Davidson, A. BAFF inhibition in SLE-Is tolerance restored? Immunol. Rev. 2019, 292, 102–119. [Google Scholar] [CrossRef] [Scilit]
- Person, T.; King, R.G.; Rizk, D.V.; Novak, J.; Green, T.J.; Reily, C. Cytokines and Production of Aberrantly O-Glycosylated IgA1, the Main Autoantigen in IgA Nephropathy. J. Interferon Cytokine Res. 2022, 42, 301–315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suzuki, Y. B cell targeting in IgA nephropathy. Nephrology 2024, 29, 39–43. [Google Scholar] [CrossRef] [Scilit]
- Floege, J.; Rauen, T.; Tang, S.C.W. Current treatment of IgA nephropathy. Semin. Immunopathol. 2021, 43, 717–728. [Google Scholar] [CrossRef] [Scilit]
- Lv, J.; Wong, M.G.; Hladunewich, M.A.; Jha, V.; Hooi, L.S.; Monaghan, H.; Zhao, M.; Barbour, S.; Jardine, M.J.; Reich, H.N.; et al. Effect of Oral Methylprednisolone on Decline in Kidney Function or Kidney Failure in Patients with IgA Nephropathy: The TESTING Randomized Clinical Trial. Jama 2022, 327, 1888–1898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Caster, D.J.; Lafayette, R.A. The Treatment of Primary IgA Nephropathy: Change, Change, Change. Am. J. Kidney Dis. 2024, 83, 229–240. [Google Scholar] [CrossRef] [Scilit]
- Schena, F.P.; Tripepi, G.; Rossini, M.; Abbrescia, D.I.; Manno, C. Randomized clinical study to evaluate the effect of personalized therapy on patients with immunoglobulin A nephropathy. Clin. Kidney J. 2022, 15, 895–902. [Google Scholar] [CrossRef] [Scilit]
- Zhao, L.; Yang, Y.; Xu, H.; Leng, W.; Xu, G. Efficacy and safety of tacrolimus-based treatment for non-rapidly progressive IgA nephropathy. Front. Pharmacol. 2023, 14, 1189608. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, J.; Zhou, Y.; Xu, X.; Huang, K.; Chen, P.; Wu, Y.; Jin, B.; Hu, Q.; Chen, G.; Zhao, S. Current knowledge of targeted-release budesonide in immunoglobulin A nephropathy: A comprehensive review. Front. Immunol. 2022, 13, 926517. [Google Scholar] [CrossRef] [Scilit]
- Hayashi, A.; Mizuno, K.; Shinkawa, K.; Sakoda, K.; Yoshida, S.; Takeuchi, M.; Yanagita, M.; Kawakami, K. Association between tonsillectomy plus steroid pulse therapy and renal outcomes in patients with IgA nephropathy: A retrospective cohort study. BMC Nephrol. 2025, 26, 484. [Google Scholar] [CrossRef] [Scilit]
- Chiarenza, D.S.; Verrina, E.E.; La Porta, E.; Caridi, G.; Ghiggeri, G.M.; Mortari, G.; Lugani, F.; Angeletti, A.; Bigatti, C. Biologics and Non-Biologics Immunosuppressive Treatments for IgA Nephropathy in Both Adults and Children. J. Clin. Med. 2024, 13, 2465. [Google Scholar] [CrossRef] [Scilit]
- Wiederrecht, G.; Lam, E.; Hung, S.; Martin, M.; Sigal, N. The mechanism of action of FK-506 and cyclosporin A. Ann. N. Y. Acad. Sci. 1993, 696, 9–19. [Google Scholar] [CrossRef] [Scilit]
- Heidt, S.; Roelen, D.L.; Eijsink, C.; Eikmans, M.; van Kooten, C.; Claas, F.H.; Mulder, A. Calcineurin inhibitors affect B cell antibody responses indirectly by interfering with T cell help. Clin. Exp. Immunol. 2010, 159, 199–207. [Google Scholar] [CrossRef] [Scilit]
- Zachova, K.; Jemelkova, J.; Kosztyu, P.; Ohyama, Y.; Takahashi, K.; Zadrazil, J.; Orsag, J.; Matousovic, K.; Galuszkova, D.; Petejova, N.; et al. Galactose-Deficient IgA1 B cells in the Circulation of IgA Nephropathy Patients Carry Preferentially Lambda Light Chains and Mucosal Homing Receptors. J. Am. Soc. Nephrol. 2022, 33, 908–917. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lafayette, R.A.; Mayer, G.; Park, S.K.; Meyer, T.W. Angiotensin II receptor blockade limits glomerular injury in rats with reduced renal mass. J. Clin. Investig. 1992, 90, 766–771. [Google Scholar] [CrossRef] [Scilit]
- Lee, B.; Holstein-Rathlou, N.H.; Sosnovtseva, O.; Sørensen, C.M. Renoprotective effects of GLP-1 receptor agonists and SGLT-2 inhibitors-is hemodynamics the key point? Am. J. Physiol. Cell Physiol. 2023, 325, C243–C256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wimbury, D.; Muto, M.; Bhachu, J.S.; Scionti, K.; Brown, J.; Molyneux, K.; Seikrit, C.; Maixnerová, D.; Pérez-Alós, L.; Garred, P. Targeted-release budesonide modifies key pathogenic biomarkers in immunoglobulin A nephropathy: Insights from the NEFIGAN trial. Kidney Int. 2024, 105, 381–388. [Google Scholar]
- Meng, H.; Li, H.; Ohe, R.; Naing, Y.A.; Yang, S.; Kabasawa, T.; Kato, T.; Osakabe, M.; Ohtake, H.; Ishida, A.; et al. Thymic stromal lymphopoietin in tonsillar follicular dendritic cells correlates with elevated serum immunoglobulin A titer by promoting tonsillar immunoglobulin A class switching in immunoglobulin A nephropathy. Transl. Res. 2016, 176, 1–17. [Google Scholar] [CrossRef] [Scilit]
- Zhuang, Y.; Lu, H.; Li, J. Advances in the treatment of IgA nephropathy with biological agents. Chronic Dis. Transl. Med. 2024, 10, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Zhang, R.; Tang, Y.; Feng, X.; Lu, X.; Zhao, M.; Jin, J.; Ji, X.; He, H.; Zhao, L. Targeted modulation of intestinal barrier and mucosal immune-related microbiota attenuates IgA nephropathy progression. Gut Microbes 2025, 17, 2458184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kawasaki, Y. Treatment strategy with multidrug therapy and tonsillectomy pulse therapy for childhood-onset severe IgA nephropathy. Clin. Exp. Nephrol. 2022, 26, 501–511. [Google Scholar] [CrossRef] [Scilit]
- Zhao, H.; Li, Y.; Sun, J.; Xu, G.; Wang, C.; Zhou, S.; Nie, S.; Li, Y.; Su, L.; Chen, R.; et al. Immunosuppression versus Supportive Care on Kidney Outcomes in IgA Nephropathy in the Real-World Setting. Clin. J. Am. Soc. Nephrol. 2023, 18, 1186–1194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hou, F.F.; Xie, D.; Wang, J.; Xu, X.; Yang, X.; Ai, J.; Nie, S.; Liang, M.; Wang, G.; Jia, N. Effectiveness of Mycophenolate Mofetil Among Patients with Progressive IgA Nephropathy: A Randomized Clinical Trial. JAMA Netw. Open 2023, 6, e2254054. [Google Scholar] [CrossRef] [Scilit]
- Gleeson, P.J.; O’Shaughnessy, M.M.; Barratt, J. IgA nephropathy in adults-treatment standard. Nephrol. Dial. Transplant. 2023, 38, 2464–2473. [Google Scholar] [CrossRef] [Scilit]
- Del Vecchio, L.; Allinovi, M.; Comolli, S.; Peiti, S.; Rimoldi, C.; Locatelli, F. Drugs in Development to Treat IgA Nephropathy. Drugs 2024, 84, 503–525. [Google Scholar] [CrossRef] [Scilit]
- Komatsu, H.; Fujimoto, S.; Sato, Y.; Yasuda, T.; Yasuda, Y.; Matsuzaki, K.; Hirano, K.; Kawamura, T.; Yokoo, T.; Suzuki, Y.; et al. Effect of tonsillectomy combined with steroid pulse therapy upon IgA nephropathy depending on proteinuria status at diagnosis: A nationwide multicenter cohort study in Japan. Clin. Exp. Nephrol. 2024, 28, 1272–1281. [Google Scholar] [CrossRef] [Scilit]
- Ismail, M.A.; Qadi, O.I.; Alsaedi, R.O.; Alghamdi, M.M.; Alotaibi, F.M.B.A.; Almutairi, M.S.; Alodah, F.M.; Alnomari, R.T.; Alsaeed, S.S.S.; Hakami, F.A.H. Evaluating the efficacy and safety of sglt2 inhibitors in patients with iga nephropathy: A systematic review. TPM–Test. Psychom. Methodol. Appl. Psychol. 2025, 32, 1938–1946. [Google Scholar]
- Kim, Y.-C.; Chin, H.J.; Koo, H.S.; Kim, S. Tacrolimus decreases albuminuria in patients with IgA nephropathy and normal blood pressure: A double-blind randomized controlled trial of efficacy of tacrolimus on IgA nephropathy. PLoS ONE 2013, 8, e71545. [Google Scholar] [CrossRef] [Scilit]
- Lafayette, R.; Kristensen, J.; Stone, A.; Floege, J.; Tesař, V.; Trimarchi, H.; Zhang, H.; Eren, N.; Paliege, A.; Reich, H.N.; et al. Efficacy and safety of a targeted-release formulation of budesonide in patients with primary IgA nephropathy (NefIgArd): 2-year results from a randomised phase 3 trial. Lancet 2023, 402, 859–870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, J.A.; Shah, N.P.; Mudano, A.S. Belimumab for systemic lupus erythematosus. Cochrane Database Syst. Rev. 2021, 2, Cd010668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allen, M.E.; Rus, V.; Szeto, G.L. Leveraging Heterogeneity in Systemic Lupus Erythematosus for New Therapies. Trends Mol. Med. 2021, 27, 152–171. [Google Scholar] [CrossRef] [Scilit]
- Mao, Y.; Zhang, C.; Xu, J.; Liu, C.; Zheng, S.G.; Yin, L. The beneficial effect of adding belimumab in severe and refractory IgA nephropathy: A case report. Pediatr. Nephrol. 2025, 40, 1903–1905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lenert, A.; Niewold, T.B.; Lenert, P. Spotlight on blisibimod and its potential in the treatment of systemic lupus erythematosus: Evidence to date. Drug Des. Dev. Ther. 2017, 11, 747–757. [Google Scholar] [CrossRef] [Scilit]
- Doggrell, S.A. Sibeprenlimab, which neutralizes A PRoliferation Inducing Ligand (APRIL), as a new approach to treating IgA nephropathy. Expert Opin. Biol. Ther. 2024, 24, 335–338. [Google Scholar] [CrossRef] [Scilit]
- Mathur, M.; Barratt, J.; Chacko, B.; Chan, T.M.; Kooienga, L.; Oh, K.H.; Sahay, M.; Suzuki, Y.; Wong, M.G.; Yarbrough, J.; et al. A Phase 2 Trial of Sibeprenlimab in Patients with IgA Nephropathy. N. Engl. J. Med. 2024, 390, 20–31. [Google Scholar] [CrossRef] [Scilit]
- Chen, B.; Zhu, Y.; Yang, Y.; Xu, G. Efficacy and safety of agents for IgA nephropathy: A network meta-analysis of randomized controlled trials. Front. Med. 2025, 12, 1515723. [Google Scholar] [CrossRef] [Scilit]
- Mathur, M.; Barratt, J.; Suzuki, Y.; Engler, F.; Pasetti, M.F.; Yarbrough, J.; Sloan, S.; Oldach, D. Safety, Tolerability, Pharmacokinetics, and Pharmacodynamics of VIS649 (Sibeprenlimab), an APRIL-Neutralizing IgG(2) Monoclonal Antibody, in Healthy Volunteers. Kidney Int. Rep. 2022, 7, 993–1003. [Google Scholar] [CrossRef] [Scilit]
- Kim, Y.G.; Alvarez, M.; Suzuki, H.; Hirose, S.; Izui, S.; Tomino, Y.; Huard, B.; Suzuki, Y. Pathogenic Role of a Proliferation-Inducing Ligand (APRIL) in Murine IgA Nephropathy. PLoS ONE 2015, 10, e0137044. [Google Scholar] [CrossRef] [Scilit]
- Robert, T.; Berthelot, L.; Cambier, A.; Rondeau, E.; Monteiro, R.C. Molecular Insights into the Pathogenesis of IgA Nephropathy. Trends Mol. Med. 2015, 21, 762–775. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kooienga, L.; Lo, J.; Lee, E.Y.; Kim, S.G.; Thomas, H.; Workeneh, B.; Agha, I.; Song, Y.; Smith, W.; van Eenennaam, H.; et al. Zigakibart demonstrates clinical safety and efficacy in a Phase 1/2 trial of healthy volunteers and patients with IgA nephropathy. Kidney Int. 2025, 108, 445–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maixnerova, D.; Tesar, V. Emerging role of monoclonal antibodies in the treatment of IgA nephropathy. Expert Opin. Biol. Ther. 2023, 23, 419–427. [Google Scholar] [CrossRef] [Scilit]
- Kowalczyk-Quintas, C.; Willen, D.; Willen, L.; Golob, M.; Schuepbach-Mallepell, S.; Peter, B.; Eslami, M.; Vigolo, M.; Broly, H.; Samy, E.; et al. No interactions between heparin and atacicept, an antagonist of B cell survival cytokines. Br. J. Pharmacol. 2019, 176, 4019–4033. [Google Scholar] [CrossRef] [Scilit]
- Lafayette, R.; Barbour, S.; Israni, R.; Wei, X.; Eren, N.; Floege, J.; Jha, V.; Kim, S.G.; Maes, B.; Phoon, R.K.S.; et al. A phase 2b, randomized, double-blind, placebo-controlled, clinical trial of atacicept for treatment of IgA nephropathy. Kidney Int. 2024, 105, 1306–1315. [Google Scholar] [CrossRef] [Scilit]
- Dhillon, S. Telitacicept: First Approval. Drugs 2021, 81, 1671–1675. [Google Scholar] [CrossRef] [Scilit]
- Cai, J.; Gao, D.; Liu, D.; Liu, Z. Telitacicept for autoimmune nephropathy. Front. Immunol. 2023, 14, 1169084. [Google Scholar] [CrossRef] [Scilit]
- Jin, Y.; Zhu, J.; Sheng, A.; Lin, Q.; Zhao, M.; He, X.; Mao, J.; Fu, H. Telitacicept as a BAFF/APRIL dual inhibitor: Efficacy and safety in reducing proteinuria for refractory childhood IgA vasculitis nephritis. Pediatr. Nephrol. 2025, 40, 2561–2569. [Google Scholar] [CrossRef] [Scilit]
- Lv, J.; Liu, L.; Hao, C.; Li, G.; Fu, P.; Xing, G.; Zheng, H.; Chen, N.; Wang, C.; Luo, P.; et al. Randomized Phase 2 Trial of Telitacicept in Patients with IgA Nephropathy with Persistent Proteinuria. Kidney Int. Rep. 2023, 8, 499–506. [Google Scholar] [CrossRef] [Scilit]
- Wu, L.; Du, X.; Lu, X. Role of telitacicept in the treatment of IgA nephropathy. Eur. J. Med. Res. 2023, 28, 369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zan, J.; Liu, L.; Li, G.; Zheng, H.; Chen, N.; Wang, C.; Xie, D.; Zuo, L.; Li, R.; Zhang, P.; et al. Effect of Telitacicept on Circulating Gd-IgA1 and IgA-Containing Immune Complexes in IgA Nephropathy. Kidney Int. Rep. 2024, 9, 1067–1071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shen, Y.; Yuan, J.; Chen, S.; Zhang, Y.F.; Yin, L.; Hong, Q.; Zha, Y. Combination treatment with telitacicept, mycophenolate mofetil and glucocorticoids for immunoglobulin A nephropathy: A case report. World J. Clin. Cases 2024, 12, 6307–6313. [Google Scholar] [CrossRef] [Scilit]
- He, Y.; Chen, S.; Liu, K.; Wu, X.; Yu, M.; Wang, W.; Peng, K.; Wang, L.; Li, G.; Xie, X.; et al. Telitacicept versus mycophenolate mofetil in IgA nephropathy: A real-world comparative study of efficacy, renal outcomes and safety. Clin. Kidney J. 2025, 18, sfaf261. [Google Scholar] [CrossRef] [Scilit]
- Weng, Q.; Ouyang, Y.; Chen, Z.; Jin, Y.; Xu, J.; Liu, J.; Wang, Z.; Ma, J.; Shi, H.; Shen, P.; et al. Efficacy and safety of telitacicept in IgA nephropathy: Real-world study outcomes. Clin. Kidney J. 2025, 18, sfaf154. [Google Scholar] [CrossRef] [Scilit]
- Xu, L.; Wu, S.; Zhang, P.; Wang, F.; Di, W.; Zhong, S.; Hou, Y.; Yang, H.; Li, G. Telitacicept treatment for recurrent IgA nephropathy after kidney transplantation. Clin. Kidney J. 2025, 18, sfaf232. [Google Scholar] [CrossRef] [Scilit]
- Ma, X.; Fu, X.; Cui, B.; Lin, H. Telitacicept for Recalcitrant Cutaneous Manifestations of Systemic Lupus Erythematosus: A Case Report and Review of the Literature. Tohoku J. Exp. Med. 2022, 258, 219–223. [Google Scholar] [CrossRef] [Scilit]
- Zeng, L.; Yang, K.; Wu, Y.; Yu, G.; Yan, Y.; Hao, M.; Song, T.; Li, Y.; Chen, J.; Sun, L. Telitacicept: A novel horizon in targeting autoimmunity and rheumatic diseases. J. Autoimmun. 2024, 148, 103291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evans, L.S.; Lewis, K.E.; DeMonte, D.; Bhandari, J.G.; Garrett, L.B.; Kuijper, J.L.; Ardourel, D.; Wolfson, M.F.; Debrot, S.; Mudri, S.; et al. Povetacicept, an Enhanced Dual APRIL/BAFF Antagonist That Modulates B Lymphocytes and Pathogenic Autoantibodies for the Treatment of Lupus and Other B Cell-Related Autoimmune Diseases. Arthritis Rheumatol. 2023, 75, 1187–1202. [Google Scholar] [CrossRef] [Scilit]
- Davies, R.; Peng, S.L.; Lickliter, J.; McLendon, K.; Enstrom, A.; Chunyk, A.G.; Blanchfield, L.; Wang, N.; Blair, T.; Thomas, H.M.; et al. A first-in-human, randomized study of the safety, pharmacokinetics and pharmacodynamics of povetacicept, an enhanced dual BAFF/APRIL antagonist, in healthy adults. Clin. Transl. Sci. 2024, 17, e70055. [Google Scholar] [CrossRef] [Scilit]
- Madan, A.; Yalavarthy, R.; Kim, D.K.; young Moon, J.; Park, I.; Mandayam, S.A.; Cortazar, F.B.; Kim, S.G.; Davies, R.H.; Enstrom, A.M. Results from longer follow-up with povetacicept, an enhanced dual BAFF/APRIL antagonist, in IgA nephropathy (RUBY-3 study): FR-PO854. J. Am. Soc. Nephrol. 2024, 35, 10.1681. [Google Scholar] [CrossRef] [Scilit]
- Madan, A.; Yalavarthy, R.; Kim, D.K.; Moon, J.-Y.; Park, I.; Mandayam, S.; Cortazar, F.; Kim, S.G.; Enstrom, A.; Thomas, H. Povetacicept for IgA Nephropathy and Primary Membranous Nephropathy. Kidney Int. Rep. 2025, 11, 106–116. [Google Scholar] [CrossRef] [Scilit]
- Anthera. Anthera Announces Top Line Final Data from the Extension Period of the Phase 2 BRIGHT-SC Study of Blisibimod in Patients with IgA Nephropathy. Available online: https://www.globenewswire.com/news-release/2017/08/28/1101012/0/en/Anthera-Announces-Top-Line-Final-Data-from-the-Extension-Period-of-the-Phase-2-BRIGHT-SC-Study-of-Blisibimod-in-Patients-with-IgA-Nephropathy.html (accessed on 28 August 2017).
- Tao, L.; Zhang, X.; Niu, X.; Liu, G.; Jiao, X.; Shao, F.; Cao, H. Efficacy and safety of telitacicept in the treatment of IgA nephropathy: A single-center, real-world study. Front. Pharmacol. 2025, 16, 1642137. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Zhang, Y.; Zhang, C. Effectiveness and safety of telitacicept in IgA nephropathy: A propensity score matching analysis with a 6-month follow-up. BMC Nephrol. 2025, 26, 546. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Y.; Tian, J.; Xiao, F.; Zheng, L.; Zhu, X.; Wu, L.; Zhao, C.; Wang, S.; Rui, K.; Zou, H.; et al. B cell-activating factor and its targeted therapy in autoimmune diseases. Cytokine Growth Factor Rev. 2022, 64, 57–70. [Google Scholar] [CrossRef] [Scilit]
- Doll, J.R.; Moreno-Fernandez, M.E.; Stankiewicz, T.E.; Wayland, J.L.; Wilburn, A.; Weinhaus, B.; Chougnet, C.A.; Giordano, D.; Cappelletti, M.; Presicce, P.; et al. BAFF and APRIL counterregulate susceptibility to inflammation-induced preterm birth. Cell. Rep. 2023, 42, 112352. [Google Scholar] [CrossRef] [Scilit]
- Hashiguchi, M.; Kashiwakura, Y.; Kanno, Y.; Kojima, H.; Kobata, T. Tumor necrosis factor superfamily member (TNFSF) 13 (APRIL) and TNFSF13B (BAFF) downregulate homeostatic immunoglobulin production in the intestines. Cell Immunol. 2018, 323, 41–48. [Google Scholar] [CrossRef] [Scilit]
- Samy, E.; Wax, S.; Huard, B.; Hess, H.; Schneider, P. Targeting BAFF and APRIL in systemic lupus erythematosus and other antibody-associated diseases. Int. Rev. Immunol. 2017, 36, 3–19. [Google Scholar] [CrossRef] [Scilit]
- Mok, C.C.; Tse, S.M.; Chan, K.L.; Ho, L.Y. Prevalence and risk factors of herpes zoster infection in patients with biopsy proven lupus nephritis undergoing immunosuppressive therapies. Lupus 2020, 29, 836–844. [Google Scholar] [CrossRef] [Scilit]
- Moszczuk, B.; Mucha, K.; Kucharczyk, R.; Zagożdżon, R. The Role of Glomerular and Serum Expression of Lymphocyte Activating Factors BAFF and APRIL in Patient with Membranous and IgA Nephropathies. Arch. Immunol. Ther. Exp. 2025, 73, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Grosserichter-Wagener, C.; Franco-Gallego, A.; Ahmadi, F.; Moncada-Vélez, M.; Dalm, V.A.; Rojas, J.L.; Orrego, J.C.; Correa Vargas, N.; Hammarström, L.; Schreurs, M.W.; et al. Defective formation of IgA memory B cells, Th1 and Th17 cells in symptomatic patients with selective IgA deficiency. Clin. Transl. Immunol. 2020, 9, e1130. [Google Scholar] [CrossRef] [Scilit]
- Zhao, Y.F.; Zhu, L.; Liu, L.J.; Shi, S.F.; Lv, J.C.; Zhang, H. Measures of Urinary Protein and Albumin in the Prediction of Progression of IgA Nephropathy. Clin. J. Am. Soc. Nephrol. 2016, 11, 947–955. [Google Scholar] [CrossRef] [Scilit]
- Yaseen, K.; Herlitz, L.C.; Villa-Forte, A. IgA Vasculitis in Adults: A Rare yet Challenging Disease. Curr. Rheumatol. Rep. 2021, 23, 50. [Google Scholar] [CrossRef] [Scilit]
- Tan, Q.; Xue, H.; Ni, X.; Fan, L.; Du, W. Comparative effectiveness and safety for the treatments despite optimized renin-angiotensin system blockade among IgA nephropathy patients at high-risk of disease progression: A network meta-analysis of randomized controlled trials. Eur. J. Intern. Med. 2023, 114, 66–73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schiemann, B.; Gommerman, J.L.; Vora, K.; Cachero, T.G.; Shulga-Morskaya, S.; Dobles, M.; Frew, E.; Scott, M.L. An essential role for BAFF in the normal development of B cells through a BCMA-independent pathway. Science 2001, 293, 2111–2114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cao, Y.; Lu, G.; Chen, X.; Chen, X.; Guo, N.; Li, W. BAFF is involved in the pathogenesis of IgA nephropathy by activating the TRAF6/NF-κB signaling pathway in glomerular mesangial cells. Mol. Med. Rep. 2020, 21, 795–805. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, X.J. Immunoglobulin A Nephropathy: Molecular Pathogenesis and Targeted Therapy. MedComm (2020) 2025, 6, e70382. [Google Scholar] [CrossRef] [Scilit]
- Bossen, C.; Cachero, T.G.; Tardivel, A.; Ingold, K.; Willen, L.; Dobles, M.; Scott, M.L.; Maquelin, A.; Belnoue, E.; Siegrist, C.A.; et al. TACI, unlike BAFF-R, is solely activated by oligomeric BAFF and APRIL to support survival of activated B cells and plasmablasts. Blood 2008, 111, 1004–1012. [Google Scholar] [CrossRef] [Scilit]
- Castigli, E.; Wilson, S.A.; Scott, S.; Dedeoglu, F.; Xu, S.; Lam, K.P.; Bram, R.J.; Jabara, H.; Geha, R.S. TACI and BAFF-R mediate isotype switching in B cells. J. Exp. Med. 2005, 201, 35–39. [Google Scholar] [CrossRef] [Scilit]
- Kiryluk, K.; Li, Y.; Scolari, F.; Sanna-Cherchi, S.; Choi, M.; Verbitsky, M.; Fasel, D.; Lata, S.; Prakash, S.; Shapiro, S.; et al. Discovery of new risk loci for IgA nephropathy implicates genes involved in immunity against intestinal pathogens. Nat. Genet. 2014, 46, 1187–1196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sallustio, F.; Curci, C.; Chaoul, N.; Fontò, G.; Lauriero, G.; Picerno, A.; Divella, C.; Di Leo, V.; De Angelis, M.; Ben Mkaddem, S.; et al. High levels of gut-homing immunoglobulin A+ B lymphocytes support the pathogenic role of intestinal mucosal hyperresponsiveness in immunoglobulin A nephropathy patients. Nephrol. Dial. Transplant. 2021, 36, 452–464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bossen, C.; Schneider, P. BAFF, APRIL and their receptors: Structure, function and signaling. Semin. Immunol. 2006, 18, 263–275. [Google Scholar] [CrossRef] [Scilit]
- Floege, J.; Bernier-Jean, A.; Barratt, J.; Rovin, B. Treatment of patients with IgA nephropathy: A call for a new paradigm. Kidney Int. 2025, 107, 640–651. [Google Scholar] [CrossRef] [Scilit]
- Walsh, M.C.; Lee, J.; Choi, Y. Tumor necrosis factor receptor- associated factor 6 (TRAF6) regulation of development, function, and homeostasis of the immune system. Immunol. Rev. 2015, 266, 72–92. [Google Scholar] [CrossRef] [Scilit]
- Tang, X.; Zhang, L.; Wei, W. Roles of TRAFs in NF-κB signaling pathways mediated by BAFF. Immunol. Lett. 2018, 196, 113–118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coppo, R. The Gut-Renal Connection in IgA Nephropathy. Semin. Nephrol. 2018, 38, 504–512. [Google Scholar] [CrossRef] [Scilit]
- He, J.W.; Zhou, X.J.; Lv, J.C.; Zhang, H. Perspectives on how mucosal immune responses, infections and gut microbiome shape IgA nephropathy and future therapies. Theranostics 2020, 10, 11462–11478. [Google Scholar] [CrossRef] [Scilit]
- Magliozzi, R.; Marastoni, D.; Calabrese, M. The BAFF/APRIL system as therapeutic target in multiple sclerosis. Expert Opin. Ther. Targets 2020, 24, 1135–1145. [Google Scholar] [CrossRef] [Scilit]
- Xu, Z.; Zhan, H.; Zhang, J.; Li, Z.; Cheng, L.; Chen, Q.; Guo, Y.; Li, Y. New biomarkers in IgA nephropathy. Clin. Immunol. 2025, 274, 110468. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suzuki, H. Biomarkers for IgA nephropathy on the basis of multi-hit pathogenesis. Clin. Exp. Nephrol. 2019, 23, 26–31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.