


Abstract
The SARS-CoV-2 pandemic has significantly impacted global health and has led the population and the scientific community to live in fear of a future pandemic. Based on viral infectious diseases, innate immunity cells such as mast cells and basophils play a fundamental role in the pathogenesis of viral diseases. Understanding these mechanisms could be essential to better study practical therapeutic approaches not only to COVID-19 but also to other viral infections widely spread worldwide, such as influenza A, HIV, and dengue. In this literature review, we want to study these concepts. Mast cells and basophils intervene as a bridge between innate and acquired immunity and seem to have a role in the damage mechanisms during infection and in the stimulation of humoral and cellular immunity. In some cases, these cells can act as reservoirs and favor the replication and spread of the virus in the body. Understanding these mechanisms can be useful not only in therapeutic but also in diagnostic and prognostic perspectives. The prospects of applying artificial intelligence and machine learning algorithms for the creation of very accurate diagnostic/prognostic tools are interesting.
1. Introduction
The COVID-19 pandemic has had a huge impact worldwide, especially regarding the mortality rate. Great interest is involved in understanding the pathogenetic mechanisms behind this condition to try to find prognostic parameters of disease that can predict severity.
In a previous work, we assessed the possibility that serum and tissue variations in basophils and mast cells could be predictors of disease severity. In detail, we observed that a reduction in basophils in the acute phase of the disease was associated with more severe COVID-19. At the same time, mast cells could represent a therapeutic target implicated in airway inflammation [1]. Furthermore, mast cells in the nasal and lung epithelium were associated with cytokine storms, inducing pulmonary fibrosis and thrombosis [2].
In recent years, the interest in pandemic or epidemic infectious diseases has gradually increased, especially in light of the growing fear of future pandemics.
In light of the potential role of these cells in the pathogenesis of SARS-CoV-2 disease, their involvement in other widely spread viral infectious diseases could be of great interest. In this work, we focused our attention on COVID-19 and other pandemic infections and the role of mast cells and basophils in the pathogenic process. In particular, research has focused on the human immunodeficiency virus (HIV), influenza A viruses (IAVs), and dengue virus, given the recent increase in cases. Furthermore, we wanted to provide an update on the role of these two cell populations in SARS-CoV-2 infection.
Our review aims to better understand the role of mast cells and basophils in the physiopathological mechanisms of the main viral diseases responsible for pandemics or which could cause them in the future. Furthermore, we want to analyse the potential role of these cells as prognostic indicators and possible therapeutic targets.
2. Materials and Methods
We performed a strategic search through PubMed to find studies regarding the role of basophils and mast cells in SARS-CoV-2, HIV, IAV, and dengue virus infection. The keywords used for the search were “basophils/mastocytes” and “HIV” or “SARS-CoV-2” or “COVID-19” or “Influenza A” or “Dengue”. We found 1250 manuscripts. We selected articles in English published up to October 2024. Considering the studies on COVID-19, we have only selected articles published after October 2021, as the previous ones were the subject of a previous review by us. The same criterion was adopted considering the topic “HIV”, since a review from 2016 is present in the literature. Therefore, we limited the search to all studies published after December 2016. After excluding duplicates, we analysed the abstract and text for each remaining article and selected 58 valuable articles. Of these studies, thirty-six involved mast cells, sixteen involved basophils, and six involved both cell types.
3. Results
3.1. Role of Mast Cells and Basophils in the Course of SARS-CoV-2 Infection
Mast cells are important sentinel cells of our immune system. They are strategically located at sites that interface with the external environment, such as the skin and mucosal surfaces of the respiratory tract and nasal cavity, to protect the body against viral and bacterial entry.
Although mast cells are known as effectors of the allergic response, they can interact with various immune cells by releasing soluble factors or by direct contact to regulate the immune response in a beneficial or harmful way. Several pathogens or their products can activate mast cells, inducing the secretion of cytokines and chemokines by degranulation-dependent or degranulation-independent pathways. The release of these inflammatory mediators contributes to the recruitment of immune effector cells to remove pathogens; however, these mediators may also promote inappropriate proinflammatory responses, contributing to the damage of epithelial–endothelial barriers and facilitating pathogens’ invasion [3].
SARS-CoV-2, through the spike protein, binds to angiotensin-converting enzyme 2 (ACE2) to enter cells, and then host serine protease transmembrane protease serine 2 (TMPRSS2) cleaves the spike protein and enables cellular membrane fusion. ACE2 and TMPRSS2 are expressed on the epithelium of the lungs, skin, and intestines. In contrast, other host molecules that may be involved in SARS-CoV-2 invasion, such as CD147 and CD26, are expressed in both epithelium and immune cells [4].
The host response to viral RNA invasion activates Toll-like receptor (TLR)-3 on mast cells with type I IFN production (beneficial effect); however, the virus can cause sensitization of mast cells with IgE production that bind to the FcεRI receptor, triggering an excessive proinflammatory reaction (harmful effect). Overall, the RNA virus causes the production of IFN-gamma e CXCL8, leading to the recruitment of NK cells that also contribute to type I IFN production. The virus can stimulate mucosal mast cells, causing the release of TNF-alpha, IL-1, IL-6, proteases (worsening the inflammatory condition), histamine, prostaglandin D2, and leukotriene C4 (inducing acute bronchoconstriction and lung inflammation) [5].
The main inflammatory cytokines and chemokines widely produced by patients with severe forms of COVID-19 are IL-6, IL-8, IL-1β, TNF-alpha, IFN-gamma, MIP1α and 1β, CCL2, CCL5, CCL20, CXCL1, CXCL2, CXCL8, CXCL10, and CXCL17. In particular, high levels of IL-6, TNF-alpha, and C-reactive protein (CRP) appear to be independent factors for the severity of COVID-19 disease [6,7,8,9,10].
Patients with mild symptoms after COVID-19 can show diffuse, multiorgan symptoms several months after the infection. These symptoms were initially reported in children and named Multisystem Inflammatory Syndrome (MIS-C), but a similar condition has also occurred in adults, named Multisystem Inflammatory Syndrome (MIS-A). The typical symptoms (malaise, chest tightness, myalgias, brain fog, and other neuropsychiatric symptoms) are very similar to those associated with Mast Cell Activation Syndrome [11].
Inspired by Murdaca et al.’s earlier work in 2021, we assessed the current state of the art in the literature on the role of mast cells in COVID-19 [1].
In a study by Li et al. [12], it was observed that patients with frailty were more prone to poor health conversions and sequelae (these adverse health transitions were significantly associated with mast cell activation).
In a mouse and non-human primate model studied by Tan et al. [13], the widespread activation of mast cells in lung tissue (densely localized and degranulating, especially within the haemorrhagic regions of infected lung) was noticed.
According to this, Gebremeskel et al. [14] have evaluated the serum of 19 SARS-CoV-2 patients and 20 uninfected controls, showing that mast cells-derived proteases and eosinophil-associated mediators are increased in COVID-19 lungs and/or serum; they also observed that mast cells activation is induced through TLR3/7/8 stimulation.
Recently, Cao et al. [15] confirmed that SARS-CoV-2 infection induces the accumulation and degranulation of mast cells in the peritrachea of mice. Indeed, mast cell activation induces the production of inflammatory factors in bronchial epithelial cells.
Otherwise, in a multicentre prospective study by MacCann et al. [16], 61 patients with COVID-19 were compared with 54 healthy controls, showing a greater downregulation of FCER1A (gene encodes for FcεRI on mast cells) in the moderate/severe COVID-19 group than the group with mild disease; a downregulation of the TNF-alpha, PTGS2, and IL1B genes in the moderate/severe COVID-19 group was also noted, suggesting the downregulation of mast cells’ activation. These events lead to a dysregulation of the antiviral response.
To verify that the interaction between spike protein and ACE2 is pivotal to activating mast cell degranulation, Wu et al. [17] attempted to block the interaction through prior treatment with an anti-ACE2 antibody, finding that spike-RBD treatment of LAD2 cells was no longer able to induce mast cells’ degranulation.
The use of mast cell stabilizers (sodium cromoglicate) and antihistamines could explain the lower incidence of severe forms of COVID-19 in atopic patients, so mast cells could potentially be a therapeutic target to avoid a worse prognosis [17]. In addition, using quercetin supplements could also modulate the inflammatory system by reducing the risk of developing severe forms of COVID-19 [18].
Murdaca et al.’s review also focused on the role of basophils in the pathogenesis of the disease, analysing the studies present in the literature up to 2021 [1]. The number of basophils is depleted during acute infection and the efficacy of humoral and cellular immune responses to SARS-CoV-2 is consequently compromised. In basophils, a reduction in the expression of surface CRTH2, a receptor for prostaglandin D2, and a significant increase in programmed cell death ligand 1 (PD-L1) were observed, especially in the most severe cases of disease. CRTH2 is a critical activator of the polarized T helper response.
In the chronic phase of the disease, on the contrary, basophils showed a progressive increase in levels with the improvement of the humoral immune response, perhaps related to the production of IL-4 by these cells [1].
In recent years, several authors have continued to focus on the direct correlation between basophils and the disease. Bonam et al. [19] demonstrated that SARS-CoV-2 stimulates the production of IL-13, both in resting basophils and in those primed by IL-3. In the same study, the authors found that neither infected epithelial cells nor the virus itself can alter the expression of CD69, CD13, and/or the degranulation marker CD107a, important surface markers associated with basophil activation. Furthermore, the same authors state that SARS-CoV-2 does not induce PD-L1 on basophils, contrary to what was found in past studies [19].
Recently, the coronavirus receptor (CoV-R) expression profiles have been studied in different cells of innate immunity and related cell lines. Basophils, in studies by flow cytometry, express CD13 and CD147 of the CoV-R, while they do not express CD26. Then, studying the drug effects on the expression of CoV-R, it was found that dexamethasone, vitamin D, and hydroxychloroquine do not affect the expression of these receptors [20].
In recent years, many authors have continued to observe the correlations between biohumoral profiles and the clinical characteristics of SARS-CoV-2 infection. Liu et al. [21] studied the profile of a group of patients admitted to C10 West Ward, Tongji Hospital in Wuhan City. From their retrospective analysis, it emerged that, among the various parameters considered, basophil levels were significantly elevated in critical patients. Above all, basophil levels were higher in the death subgroup compared to the survival subgroup.
By retrospectively studying the cellular profiles of patients before and after contracting the disease, it was also demonstrated that those with higher levels of basophils and monocytes were at greater risk of contracting the severe infection [22].
In contrast, in the retrospective study by Binsaleh et al. [23] on a Saudi Arabian population of 108 hospitalized COVID-19 patients, disease-related mortality was significantly associated with reduced basophils.
In support of this, the study by Ben et al. [24] demonstrated that individuals with non-severe disease show reduced levels of basophils and basophilic aminotransferases (%) compared to healthy subjects.
Moreover, studies by Rauf Saeed and Lal on 105 Pakistani patients did not demonstrate any correlation between basophils and disease severity [25].
In recent years, the application of artificial intelligence to studying various pathological conditions has become increasingly attractive [26]. Through machine learning (ML), we can research and combine large amounts of data and create precise predictive algorithms. Many authors have exploited these tools to obtain instruments capable of predicting the risk of hospitalization or mortality from disease.
Fu et al. [27] applied the LASSO logistic regression-based predictive model to a database of 1929 patients with COVID-19. The ML model identified 28 variables useful for the prognosis of critical illness, and among them, a low basophil count is associated with the development of critical illness at the time of hospital admission.
Chadaga et al.’s model also allowed the use of different peripheral blood markers to stratify SARS-CoV-2 patients’ risks, with overlapping results [28].
Unsupervised clustering analysis with neural network self-organizing maps was used to identify potential variables in routine blood tests that can help identify COVID-19 infection at the time of hospital admission. Variables such as the number of leukocytes, basophils, eosinophils, and red blood cell distribution width showed a strong influence on the clustering performance [29].
Wang and his group [30] developed and validated a multivariate model based on complete blood count to predict recovery from moderate disease. Their model used data from 86 patients and 38 patients from another hospital for external verification of the model. The logistic regression model identified basophil levels’ mean corpuscular volume, red blood cell distribution width, and platelet distribution width as valuable parameters for predicting recovery. Indeed, small increases in these parameters within the normal range correspond to clinical improvement in these patients.
Min Baik et al. [31] developed models based on eXtreme gradient boosting, category boosting, and light gradient boosting machines to easily differentiate COVID-19 pneumonia from other forms of pneumonia. Among the various parameters used, basophil seemed to be one of the most important features in differentiating the two groups of diseases.
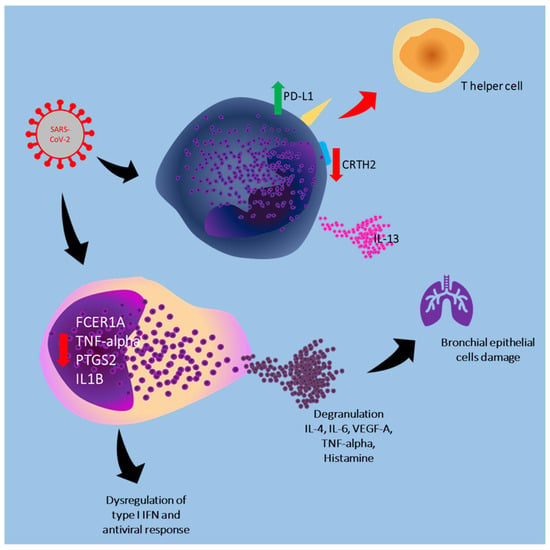
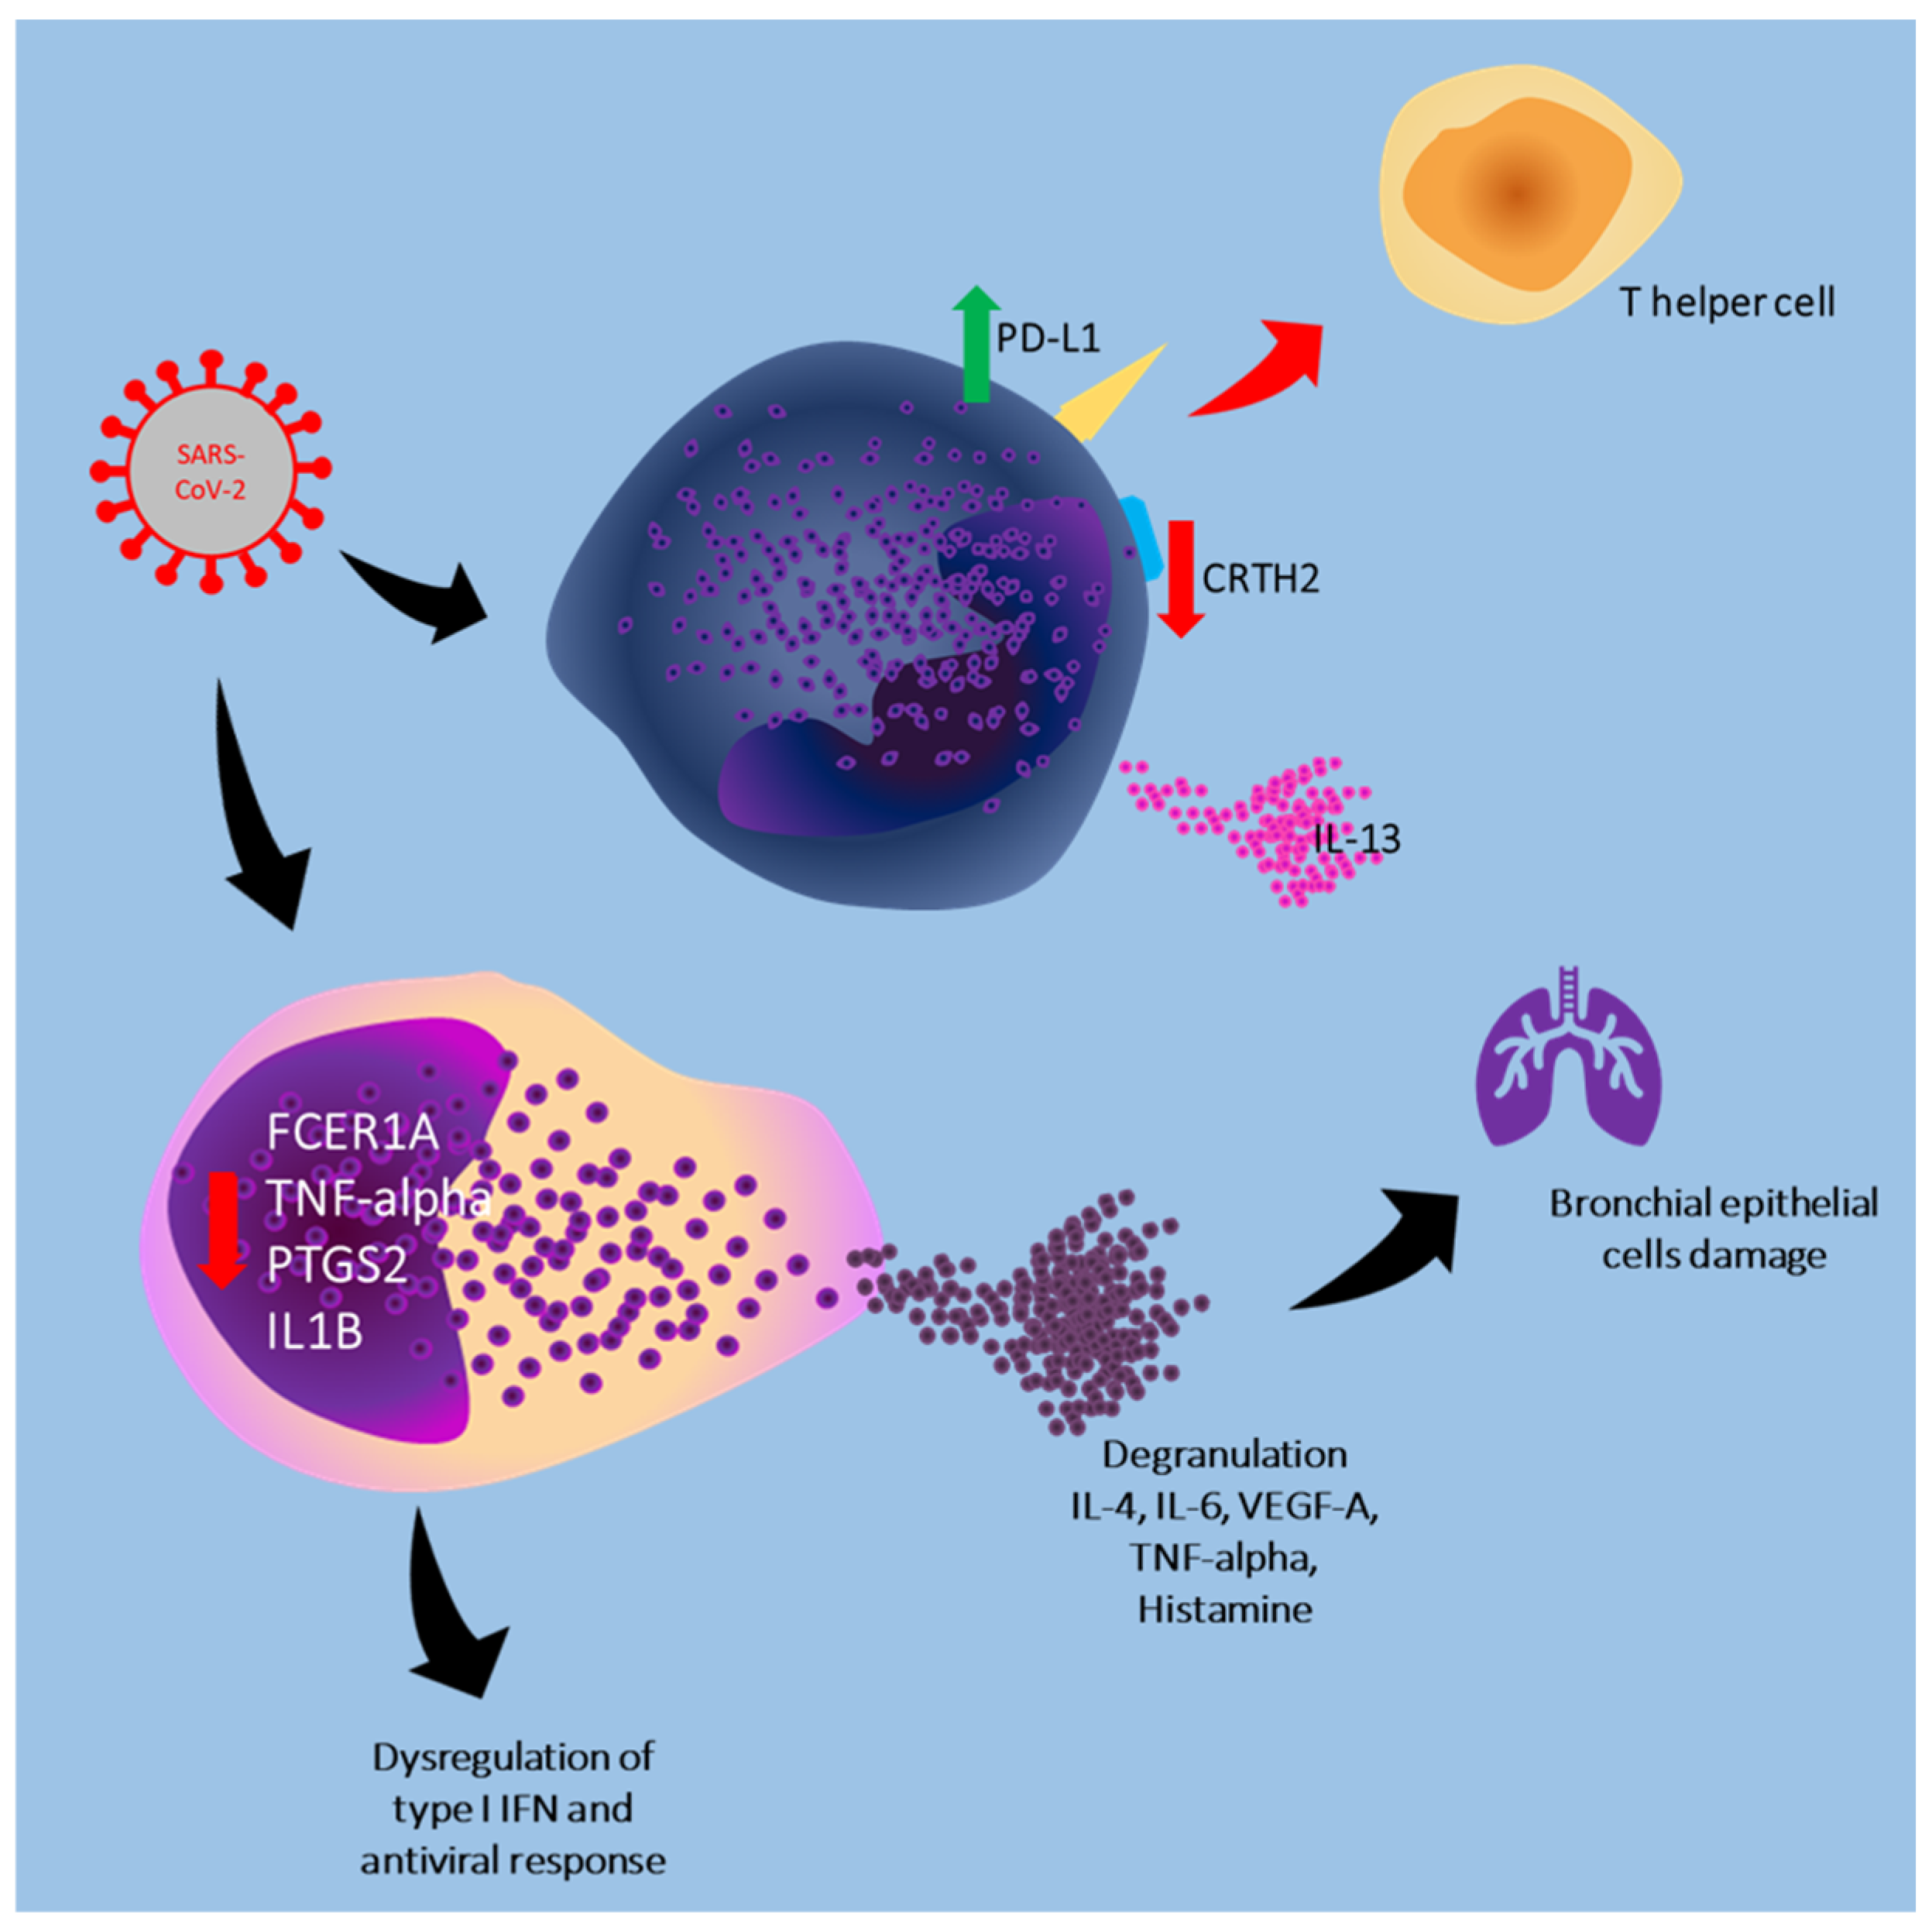
Figure 1 summarizes the mechanisms through which SARS-CoV-2 interacts with mast cells and basophils.
Figure 1.
In the active phases of infection, the virus causes a reduction in the expression of CRTH2 on the surface of basophils and a significant increase in PD-L1, reducing the activation of the polarized T helper response. Active mast cells of the bronchial mucosa release TNF-alpha, IL-1, IL-6, proteases, histamine, prostaglandin D2, and leukotriene C4, promoting lung damage. In addition, the altered gene expressions induced by the virus significantly reduce the antiviral response of the immune system dependent on type I INF; The green arrow indicates an increase, the red arrows indicate a decrease.
Table 1 summarizes data from studies on the role of mast cells and basophiles.
Table 1.
Mast cells and basophils in SARS-CoV-2 infection.
3.2. Role of Mast Cells and Basophils in the Course of Influenza a Virus Infection
Influenza viruses cause recurrent upper and/or lower respiratory tract diseases, with symptoms ranging from simple nasopharyngitis to pneumonia. It can also cause acute respiratory distress syndrome and rarely lead to death from respiratory failure. Influenza viruses usually appear in more or less large population groups (epidemic outbreaks), but they can sometimes spread to a larger population and cause pandemics. Viruses that can cause contagious respiratory diseases are influenza A (IAV) and influenza B (IBV), belonging to the Orthomyxoviridae family [32]. These viruses are divided into subgroups based on the antigenic properties of their surface proteins: hemagglutinin and neuraminidase. IAVs are not exclusive to humans but can infect animals and subsequently be transmitted to humans through zoonoses. IAVs tend to spread periodically as seasonal viruses, causing more or less extensive epidemic outbreaks. However, in the past, IAVs have been responsible for four pandemics: the “Spanish flu” of 1918 (H1N1), the “Asian flu” of 1957 (H2N2), the “Hong Kong flu” of 1968 (H3N2), and the influenza A pdm09 from 2009 to 2010 (H1N1) [33].
The innate immune response to IAVs is complex and poorly understood. The protagonists of the immune response can be responsible for abnormal responses, which can cause serious clinical conditions.
In literature, several authors have studied the role of different cells of innate immunity in the pathogenesis of the infection, often to find valid therapeutic targets.
The role of mast cells in the innate response against influenza viruses is unclear. Still, different viruses can induce distinct antiviral gene expression and cytokine profiles in mast cells in response to infection [34].
Mast cells play a key role in the early stages of H5N1 infection, especially in the pathogenesis of lung injury. In 2012, Hu et al. [35] studied the activity of mast cells infected by the H5N1 influenza virus in vitro (P815 cell line) and in vivo (mice). The virus can activate the mast cell, stimulating its proliferation and the release of inflammatory mediators such as histamine, tryptase, and especially IFN-gamma.
IFN-gamma released in large quantities induces apoptosis of lung epithelial cells, causing lung damage.
Subsequently, Graham et al. [36] identified a unique inflammatory cascade activated during influenza A virus infection. Indeed, in this study, A/WSN/33 induced mouse mast cells release of histamine, chemokines, cytokines, and leukotrienes. This cytokine production is dependent on RIG-I/MAVS, whereas histamine production is independent of this mechanism. Furthermore, in vivo studies have shown that respiratory infection with the same virus induces a mild disease in genetically mast cell-deficient mice.
Moreover, another pathway involved is TRL-3. A study on P815 cells infected with the influenza A virus has demonstrated how this pathway determines the production of proinflammatory cytokines and chemokines such as IL-6, IFN-gamma, TNF-alpha, CCL-2, CCL-5, and IP-10 [37]. Furthermore, according to the same authors, mast cells, in addition to actively participating in the immune response, would be a reservoir for viral replication.
Liu et al. [38] tried to analyse the inflammatory response following influenza A infection in the P815 cell line. H5N1 and H7N2 viruses would induce mast cell apoptosis through the intrinsic mitochondria/cytochrome c-mediated pathway. Furthermore, the authors demonstrated how inhibiting the virus-induced apoptotic mechanism reduced proinflammatory cytokines and viral replication.
Desheva and her team [39] obtained a contrasting result. They studied the role of these cells in immunized mice compared to a control group. Vaccination significantly reduces the risk of lethal infection. Furthermore, when comparing the lungs of vaccinated mice to the control group, the number of mast cells and the amount of released histamine were significantly increased.
Demonstrating the key role of mast cells in the pathogenesis of airway damage following influenza A virus infection is a study on the efficacy of sodium cromoglicate in the treatment of the disease. Sodium cromoglicate is a mast cell stabilizer. Han et al. [40] studied the airways of mice infected with the H5N1 virus and treated with sodium cromoglicate. Not only did these mice have a higher survival rate from the disease, but reduced expression of IL-6, TNF-alpha, Toll-like receptor 3, and TRIF (TIR domain-containing adaptor-inducing interferon-β) was demonstrated in the lungs of sodium cromoglicate-treated mice.
In a more recent study, Huo et al. [41] demonstrated how melatonin influences mast cells activity. In fact, melatonin is a potent antioxidant and anti-inflammatory molecule with antiviral properties. In their study, the authors noted that melatonin-deficient mice infected with H1N1 had a significantly higher mortality rate reduced by melatonin administration. Melatonin determines the down-regulation of the HIF-1 pathway and the inhibition of proinflammatory cytokines release by mast cells, inhibiting the migration and activation of neutrophils and macrophages.
This study also indirectly provides evidence of the critical role of mast cells in determining damage during influenza A virus infection.
Recently, the genetic expression of mast cells infected by Influenza A viruses was demonstrated to be different from that of non-infected cells.
Huo et al. [42] analysed different expression genes in mouse P815 cells infected by three subtypes of influenza A virus (H1N1, H5N1, and H7N2) and studied the related functions and pathways.
The authors found substantial differences between P815 cells and not-infected mast cells, particularly in H1N1- and H7N2-infected cells.
These viruses triggered many different signalling pathways, while the pathways found in H1N1 infection were limited.
This study demonstrated the essential role of 5-hydroxytryptamine (5-HT) and cGMP/PKG signalling pathways in mast cells infected with the H1N1 and H7N2 viruses.
The analysis of the mast cell proteome gave us important information about the role of these cells in the pathogenesis of influenza A. In particular, Wu et al. [43] characterized the proteome of human mast cells infected by H1N1 and H5N1 viruses, discovering forty-one differentially expressed proteins. Furthermore, they found that the H1N1 virus led to an up-regulation of the CCR4-NOT transcription complex subunit 4, regulating the RNA degradation in mast cells in this way. Instead, the H5N1 virus down-regulates the p53-signalling pathway, suppressing apoptosis.
Tang and his group [44] recently studied the transcriptomic profile of murine mast cells infected by H1N1 and H5N1 viruses. This study identified signalling pathways that are differently expressed in the two infections. Precisely, H1N1 infection activates the foxO signalling pathway and the autophagy pathway. The foxO pathway mediates anti-apoptotic and anti-inflammatory responses, explaining why H1N1 infection is less intense than H5N1. In contrast, H5N1 infection favours the expression of NF-κB, an essential regulator of the inflammatory response and the necrosis pathway. This study, therefore, demonstrates how H5N1 activates mast cells to a greater extent than H1N1 [44].
Another key point from this study is the importance of the Nbeal2 gene. This gene is necessary for developing granules and would be involved in mast cell activation. From the analysis of the transcriptomic profile, the Nbeal2 gene is more expressed by H5N1 infected mast cells, explaining why this infection tends to be more severe than that by H1N1 [44].
Few studies have examined the role of basophils in the pathogenesis of influenza A. Clementsen and his group have extensively studied the role and activity of basophils in influenza A virus infection in the past.
Already in 1989, he discovered the virus’s ability to enhance histamine release from infected human basophils through the activity of viral neuraminidase [45].
A year later, the results were reconfirmed through a study on cells treated with anti-neuraminidase antibodies, which completely abolished the virus’s effect on histamine release [46]. The same effect was obtained using antibodies against viral hemagglutinin, demonstrating their importance in the viral mechanisms enhancing histamine release [46].
Furthermore, carbohydrates would help reduce the influenza virus’s effect on histamine release since they would block the same binding sites exploited by the virus [47].
In vitro studies by Huftel et al. [48] provided further evidence of the ability of influenza A virus to induce histamine release from antigen-stimulated human basophils. In addition, incubating human leukocytes with the virus also promotes the generation of leukotrienes (LTC4). Even more interestingly, they found that eliminating T cells from the mixture before incubation obliterated these effects, demonstrating the importance of these cells in the pathogenesis of the disease.
In a recent study, it was demonstrated that a low basophil count, associated with low levels of aspartate aminotransferase and low-density lipoprotein cholesterol, were associated with the most severe forms of influenza A H1N1pdm09 [49].
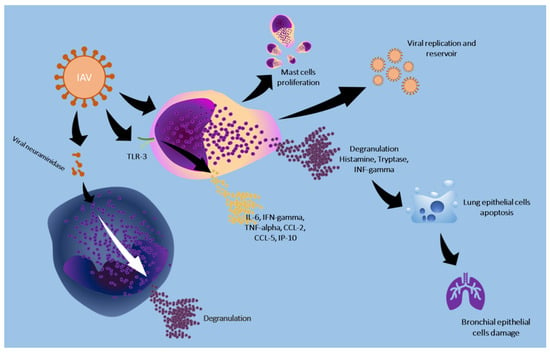
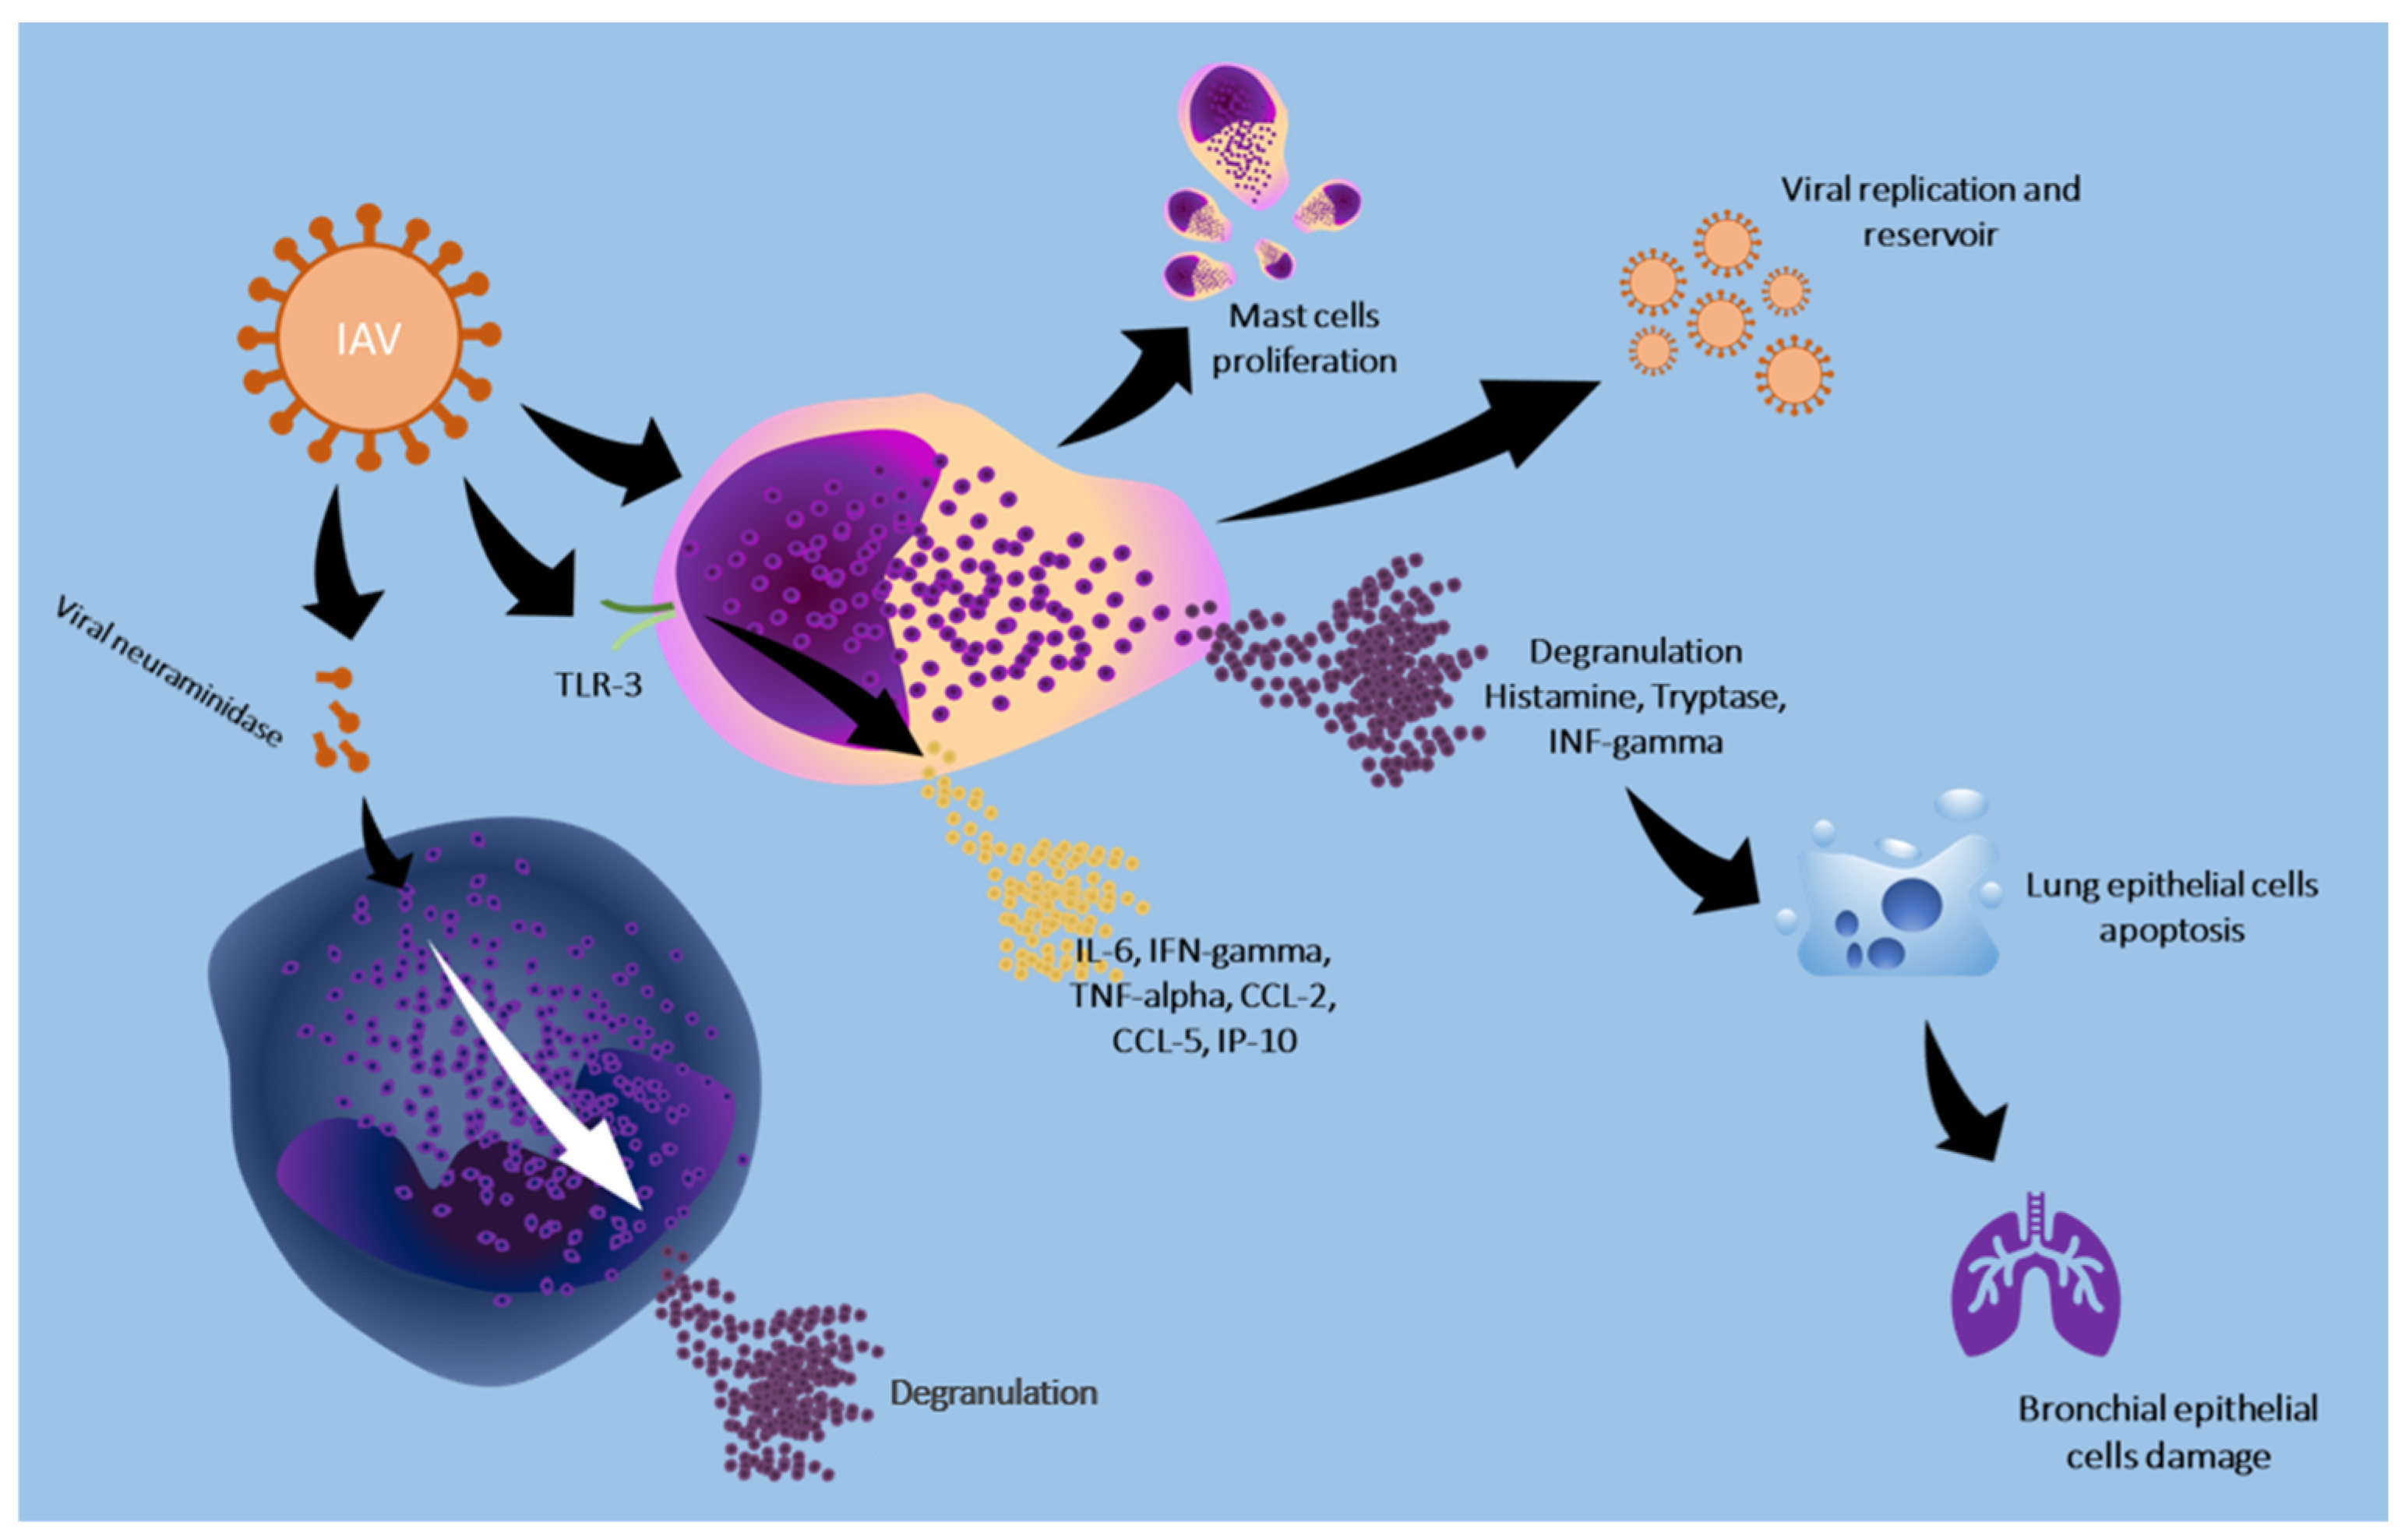
Figure 2 schematizes the effect of IVAs on mast cells and basophils.
Figure 2.
IAV causes mast cell degranulation and the release of proinflammatory cytokines through the interaction between viral proteins and TLR-3. The release of inflammatory mediators damages the respiratory epithelium and releases viruses, perpetuating the infection. Viral neuraminidases can also promote basophil degranulation, releasing other proinflammatory factors.
Table 2 summarizes data about the role of mast cells and basophils in IAV infection.
Table 2.
Mast cells and basophils in IAV infection.
3.3. Role of Mast Cells and Basophils in the Course of HIV Infection
Human immunodeficiency virus infection has long been a global public health problem, so much so that it has been considered a pandemic. It is responsible for the acquired immunodeficiency syndrome (AIDS).
Even though antiretroviral treatment reduces AIDS-related deaths, access to therapy is not equal worldwide and the prospects of curative treatments or an effective vaccine are still uncertain; as such, AIDS will continue to represent a significant public health burden [50,51].
The pathogenic mechanisms underlying infection and disease are complex and involve innate and acquired immunity.
Recent studies have shown that both basophils and mast cells capture HIV and promote trans-infection of CD4+ T cells through interaction with four proteins (gp120, gp41, Tat, and Nef) [52].
Despite numerous studies, the role of mast cells and basophils remains unclear.
A 2016 literature review [52] highlighted the potential role of these cells in the infectious process. Indeed, mast cells and basophils exposed to the virus can interact with several HIV proteins, regulating their response to infection. The key element that emerged from this review was the ability of these cells, demonstrated in numerous in vitro experiments, to transfer the virus to CD4+ T cells, thus providing a means for the virus to spread [52].
A recent review has also highlighted the role of basophils in the pathogenesis of the disease. Although considered minor players in the infectious process, these cells have been shown to have a central role since their activation creates a cascade of immune events and influences immune modulation, cytokine release, and activation of other cells of the adaptive immune system [53].
Since the 2000s, some works have demonstrated the virus’s role in inducing these cells’ degranulation. In fact, it was noted that in patients with HIV, serum IgE levels were elevated and allergic reactions were more frequent [54]. Marone et al. [55,56,57] demonstrated, through in vitro experiments, that HIV-1 gp 120 interacting with the VH3 region of IgE induced the release of inflammatory mediators by human mast cells and basophils. Furthermore, through in vitro studies, the same authors discovered how the Tat protein expressed by the virus stimulated the chemokine receptor CCR3 present in these cells, inducing its expression, influencing cell migration, and promoting the release of IL-4 and IL-13 [55,56,57].
In the same years, studies by Li et al. [58] also confirmed the susceptibility of human mast cells and basophils to HIV-1. In the peripheral blood of infected patients, they found metachromatic CD4+/CCR3+/CCR5+/CXCR4+ cells expressing the receptors for IgE FcεRI. During an allergic reaction, these cells would be able to release not only TNF-alpha and other inflammatory mediators but also the virus, exacerbating the infection [58].
In addition to gp41 and Tat, the Nef protein plays a role in HIV-1 pathogenesis. This protein is produced during the early stages of infection to create the optimal microenvironment for viral replication. Rossi et al. [59] studied the interaction between Nef, human basophils, and mast cells.
Their in vitro studies showed that incubating these cells with Nef stimulates the release of some chemokines (CXCL8/IL-8 and CCL3/MIP-1α), thus favouring the direct recruitment and activation of basophils and mast cells at the sites of viral replication.
The IgE-FcεRI interaction seems important, which would positively regulate the functional expression of CXCR4 on progenitor mast cells (prMC) [60]. Indeed, there are HIV variants that have a different tropism for different chemokines. CCR5-tropic variants (R5 viruses) bind CCR5, CXCR4-tropic variants (X4 viruses) bind CXCR4 and R5X4 viruses can bind both. IgE-FcεRI interactions during the mast cell ontogenesis phase increase the susceptibility of prMC to X4 and R5X4 viruses. Moreover, this effect is completely inhibited by using specific CXCR4 peptide antagonists or omalizumab (anti-IgE antibody). Thus, elevated IgE levels in HIV-positive and allergic individuals would influence the composition of viral variants stored in the tissue reservoir of long-lived mast cells [60].
Recently, Song et al. [61] identified the specific role of mast cells in acute retrovirus infection. Using a mouse model of MuLV/Friend virus infection, they demonstrated that this virus triggers mast cell degranulation, activating granulocyte-like myeloid-derived suppressor cells (G-MDSCs). These cells suppress CD8+ T-cell and NK-cell-mediated antiviral immune responses. Furthermore, the administration of mast cell stabilizers stimulates antiviral immune responses by suppressing retroviral infection [61].
One of the major chronic complications of HIV-infected patients is chronic lung disease, in which lung mast cells play a key pathogenetic role. Human lung mast cells (HLMC) express FcεRI, and it seems that the interaction with the superantigen gp120 expressed by the virus causes the release of proinflammatory mediators from HLMC. In the studies of Marone et al. [62], incubation of HLMC with gp120 also induced the release of angiogenic and lymphangiogenic factors from these cells through the interaction of gp120 with IgE VH3+ bound to FcεRI.
The role of mast cells in the pathogenesis of the disease has been better studied than that of basophils. Furthermore, a recent review of the literature has highlighted how many mast cells can be useful in the diagnosis and prognosis of the disease [63]. Among these, high levels of CD117 (c-kit) are correlated with increased proliferation and activation of mast cells in these patients, as well as high levels of tryptase reflecting disease progression or high levels of chymase (an index of fibrosis and remodelling) reflecting the state of possible complications [63].
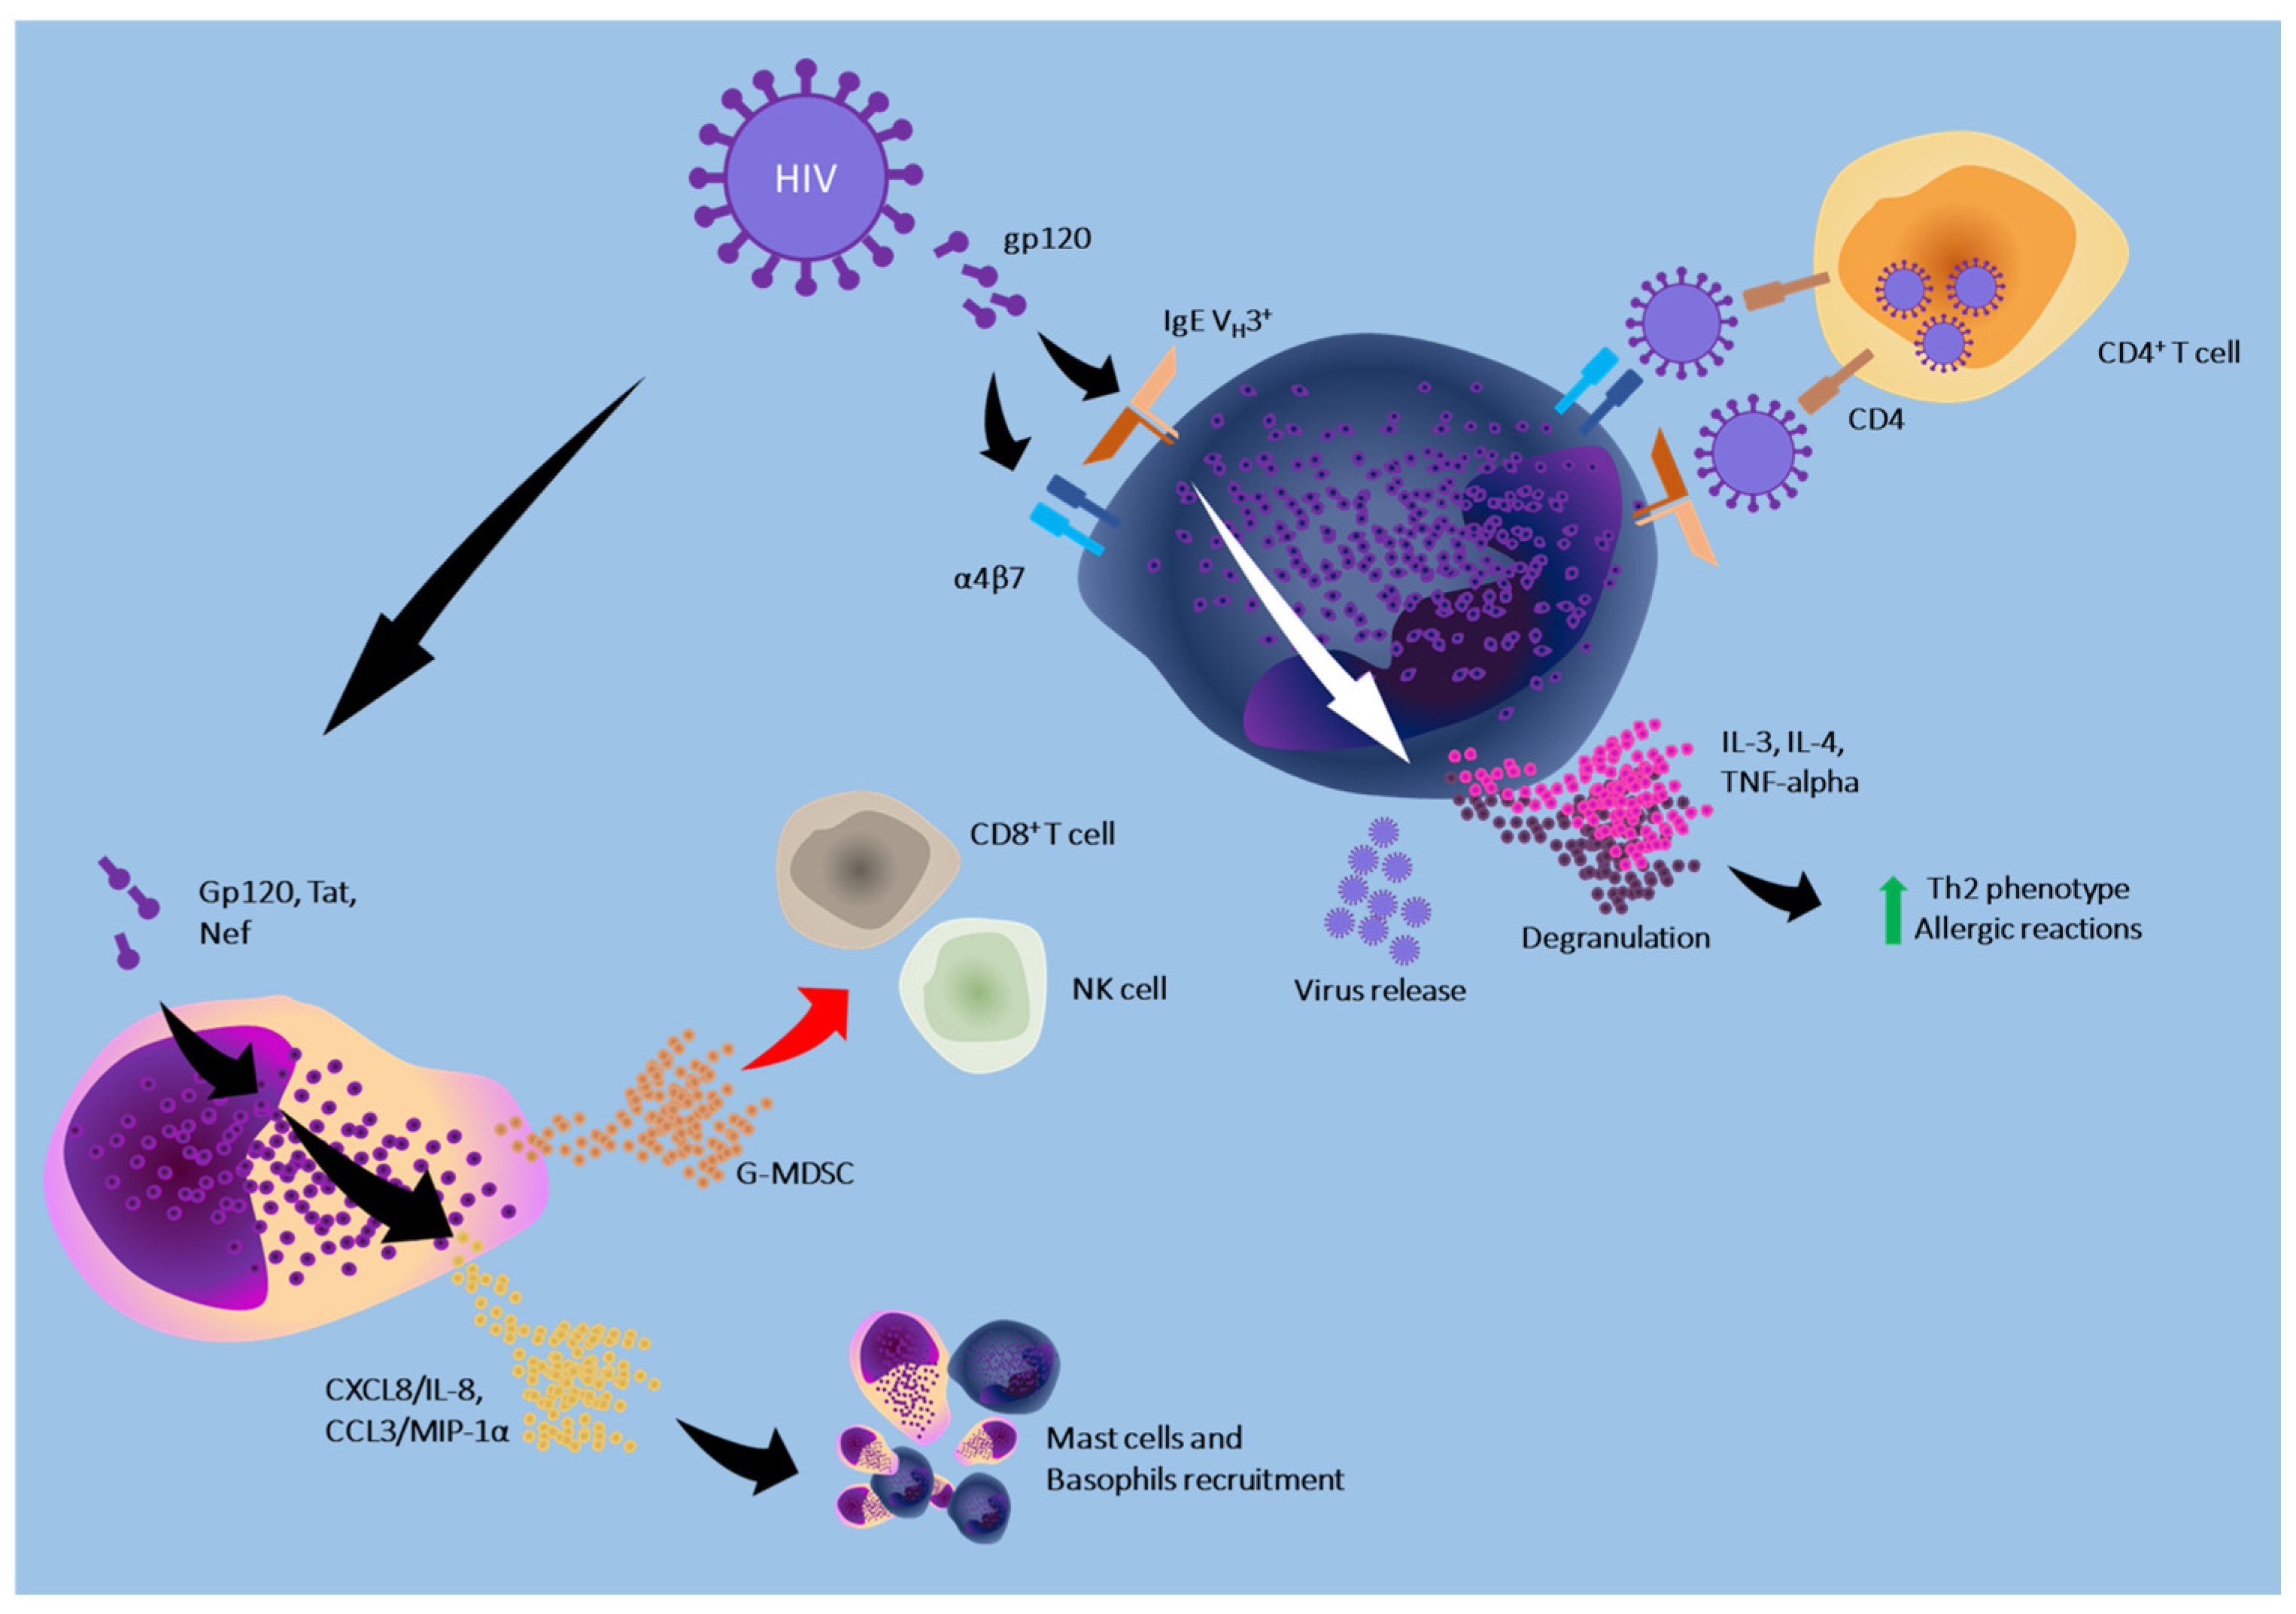
Figure 3 represents the mechanisms through which HIV interacts with mast cells and basophils.
Figure 3.
The gp120 protein expressed on the virus interacts with the VH3+ region of IgE and with α4β7 on the basophil surface, creating bridges through which the virus infects the CD4+ T lymphocyte. The same receptors also stimulate mast cell degranulation and release factors promoting the Th2 inflammatory phenotype. In this way, allergic phenomena are favoured. The gp120 protein, Tat, and Nef stimulate the release of chemokines by the mast cell, favouring the recruitment of mast cells and basophils and amplifying the response. In addition, the mast cell releases G-MDSC, a factor that inhibits the antiviral activity mediated by CD8+ T cells and NK cells; The green arrow indicates an increase, the red arrow indicates a decrease.
Table 3 summarizes all the works regarding the role of mast cells and basophils in the infection.
Table 3.
Mast cells and basophils in HIV infection.
3.4. Role of Mast Cells and Basophils in Dengue Virus Infection
The dengue virus is a single-stranded RNA virus caused by the bite of the mosquito Aedes aegypti, which deposits virus particles in the skin. It is distributed in tropical and subtropical areas and could potentially become a public health problem in Italy, given the increase in cases during 2024 and in consideration of the ongoing climate change [64]. Clinically, dengue can occur asymptomatically until the most severe cases, in which it causes a haemorrhagic fever with shock [65].
It would appear that mast cells are involved in the immune response during dengue infection, as high levels of histamine have been found in the blood and urine of patients with dengue haemorrhagic fever [66]. This hypothesis is supported by the fact that the initial site of infection of the dengue virus is the skin, which is, therefore, the first critical organ in the immune response to the virus and with it also the resident cells, such as skin mast cells [67]. Furthermore, endothelial cells infected with dengue virus produce chemokines that recall and activate mast cells [68].
Mast cell involvement has been related not simply to the immune response during dengue virus infection but specifically to the course and prognosis of the infection.
The role of mast cells in immune surveillance against the dengue virus would appear to unfold in several ways: through the release of preformed mediators, through the modification of gene expression by the production of chemokines that attract other immune cells, and through the recruitment of NK cells, which facilitate viral clearance [69].
A study in mice demonstrated mast cells’ crucial role in dengue’s course and prognosis. Mast cell-deficient mice inoculated with the virus exhibited increased viral replication, bleeding time, and worse prognosis than infected mice with normal mast cell numbers [70].
Mast cells fulfil their role as effectors of innate immunity in response to viral infection through the secretion of various mediators, including TNF-alpha, CCL4 and 5, and IFN-I, which all contribute to the immunoregulatory action by recruiting other cells affecting immunity, such as T lymphocytes, monocytes, and NK cells. The production of IFN-I is enough to safeguard the surrounding cells from infection [71] and to promote antiviral activity against the dengue virus [72]. Mice lacking IFN-I and II are more susceptible to dengue virus infection and have comorbidities, except for mice born from immunized mothers, despite the immunocompromise above. Moreover, it has been noted that the expression of IFN-gamma alone in the absence of IFN-I correlates with greater disease severity and increased mortality [73]. The CCL4 and five chemokines appear to have a positive prognostic significance, as their levels are reduced in patients with dengue haemorrhagic fever [74,75]. In response to dengue infection, mast cells and basophils also produce other chemokines, such as RANTES and MIP-1, that recruit effector T cells [76].
However, some studies demonstrate the role of dengue virus-infected mast cells in activating endothelial cells via increased TNF-alpha in the absence of increased permeability, whereby other mediators and interaction with other cells are required. TNF-alpha is thought to be primarily responsible for endothelial remodelling and plasma leakage in vivo during severe dengue infection [77]; chymase also contributes to dengue virus-induced vascular leakage [78] and it has been proposed as a predictive biomarker of dengue haemorrhagic fever [79,80]. Furthermore, leukotrienes and proteases released by mast cells contribute to endothelial loss. The absence of mast cells appears to be related to reduced vascular permeability during dengue infection [81]. Tryptase is a serine protease released exclusively by mast cells that contributes to the degradation of fibrinogen and coagulation factors and would appear to play a pivotal role in dengue virus-induced vascular permeability [82], especially in its alpha isoform [83]. Serotonin released by mast cells also contributes to dengue haemorrhagic fever by binding to 5HT2 receptors on platelets, which become activated, aggregate, and are sequestered by the spleen resulting in thrombocytopenia [84].
Therefore, several mediators released by mast cells and basophils, including vasoactive mediators, act in concert to determine endothelial damage in the most severe forms of dengue [85].
Mast cell activation during dengue virus infection is antibody-mediated. FcεRII receptor in its two different isoforms regulates mast cell activation and the release of mediators such as CCL5 [86]. Mast cell activation and degranulation mediated by preexisting anti-dengue antibodies could correlate with more severe forms of secondary dengue infection. Disease severity correlates with levels of phospholipase A2, whose activity is linked to that of PAF, a mediator that contributes to vascular damage in dengue haemorrhagic fever [87].
Most studies have focused on the role of mast cells in dengue virus infection, their interplay with other cells, and the correlation between mediators and cytokines released by mast cells and the course and prognosis of infection. Currently, the role of basophils in the course of dengue infection is limited and poorly understood.
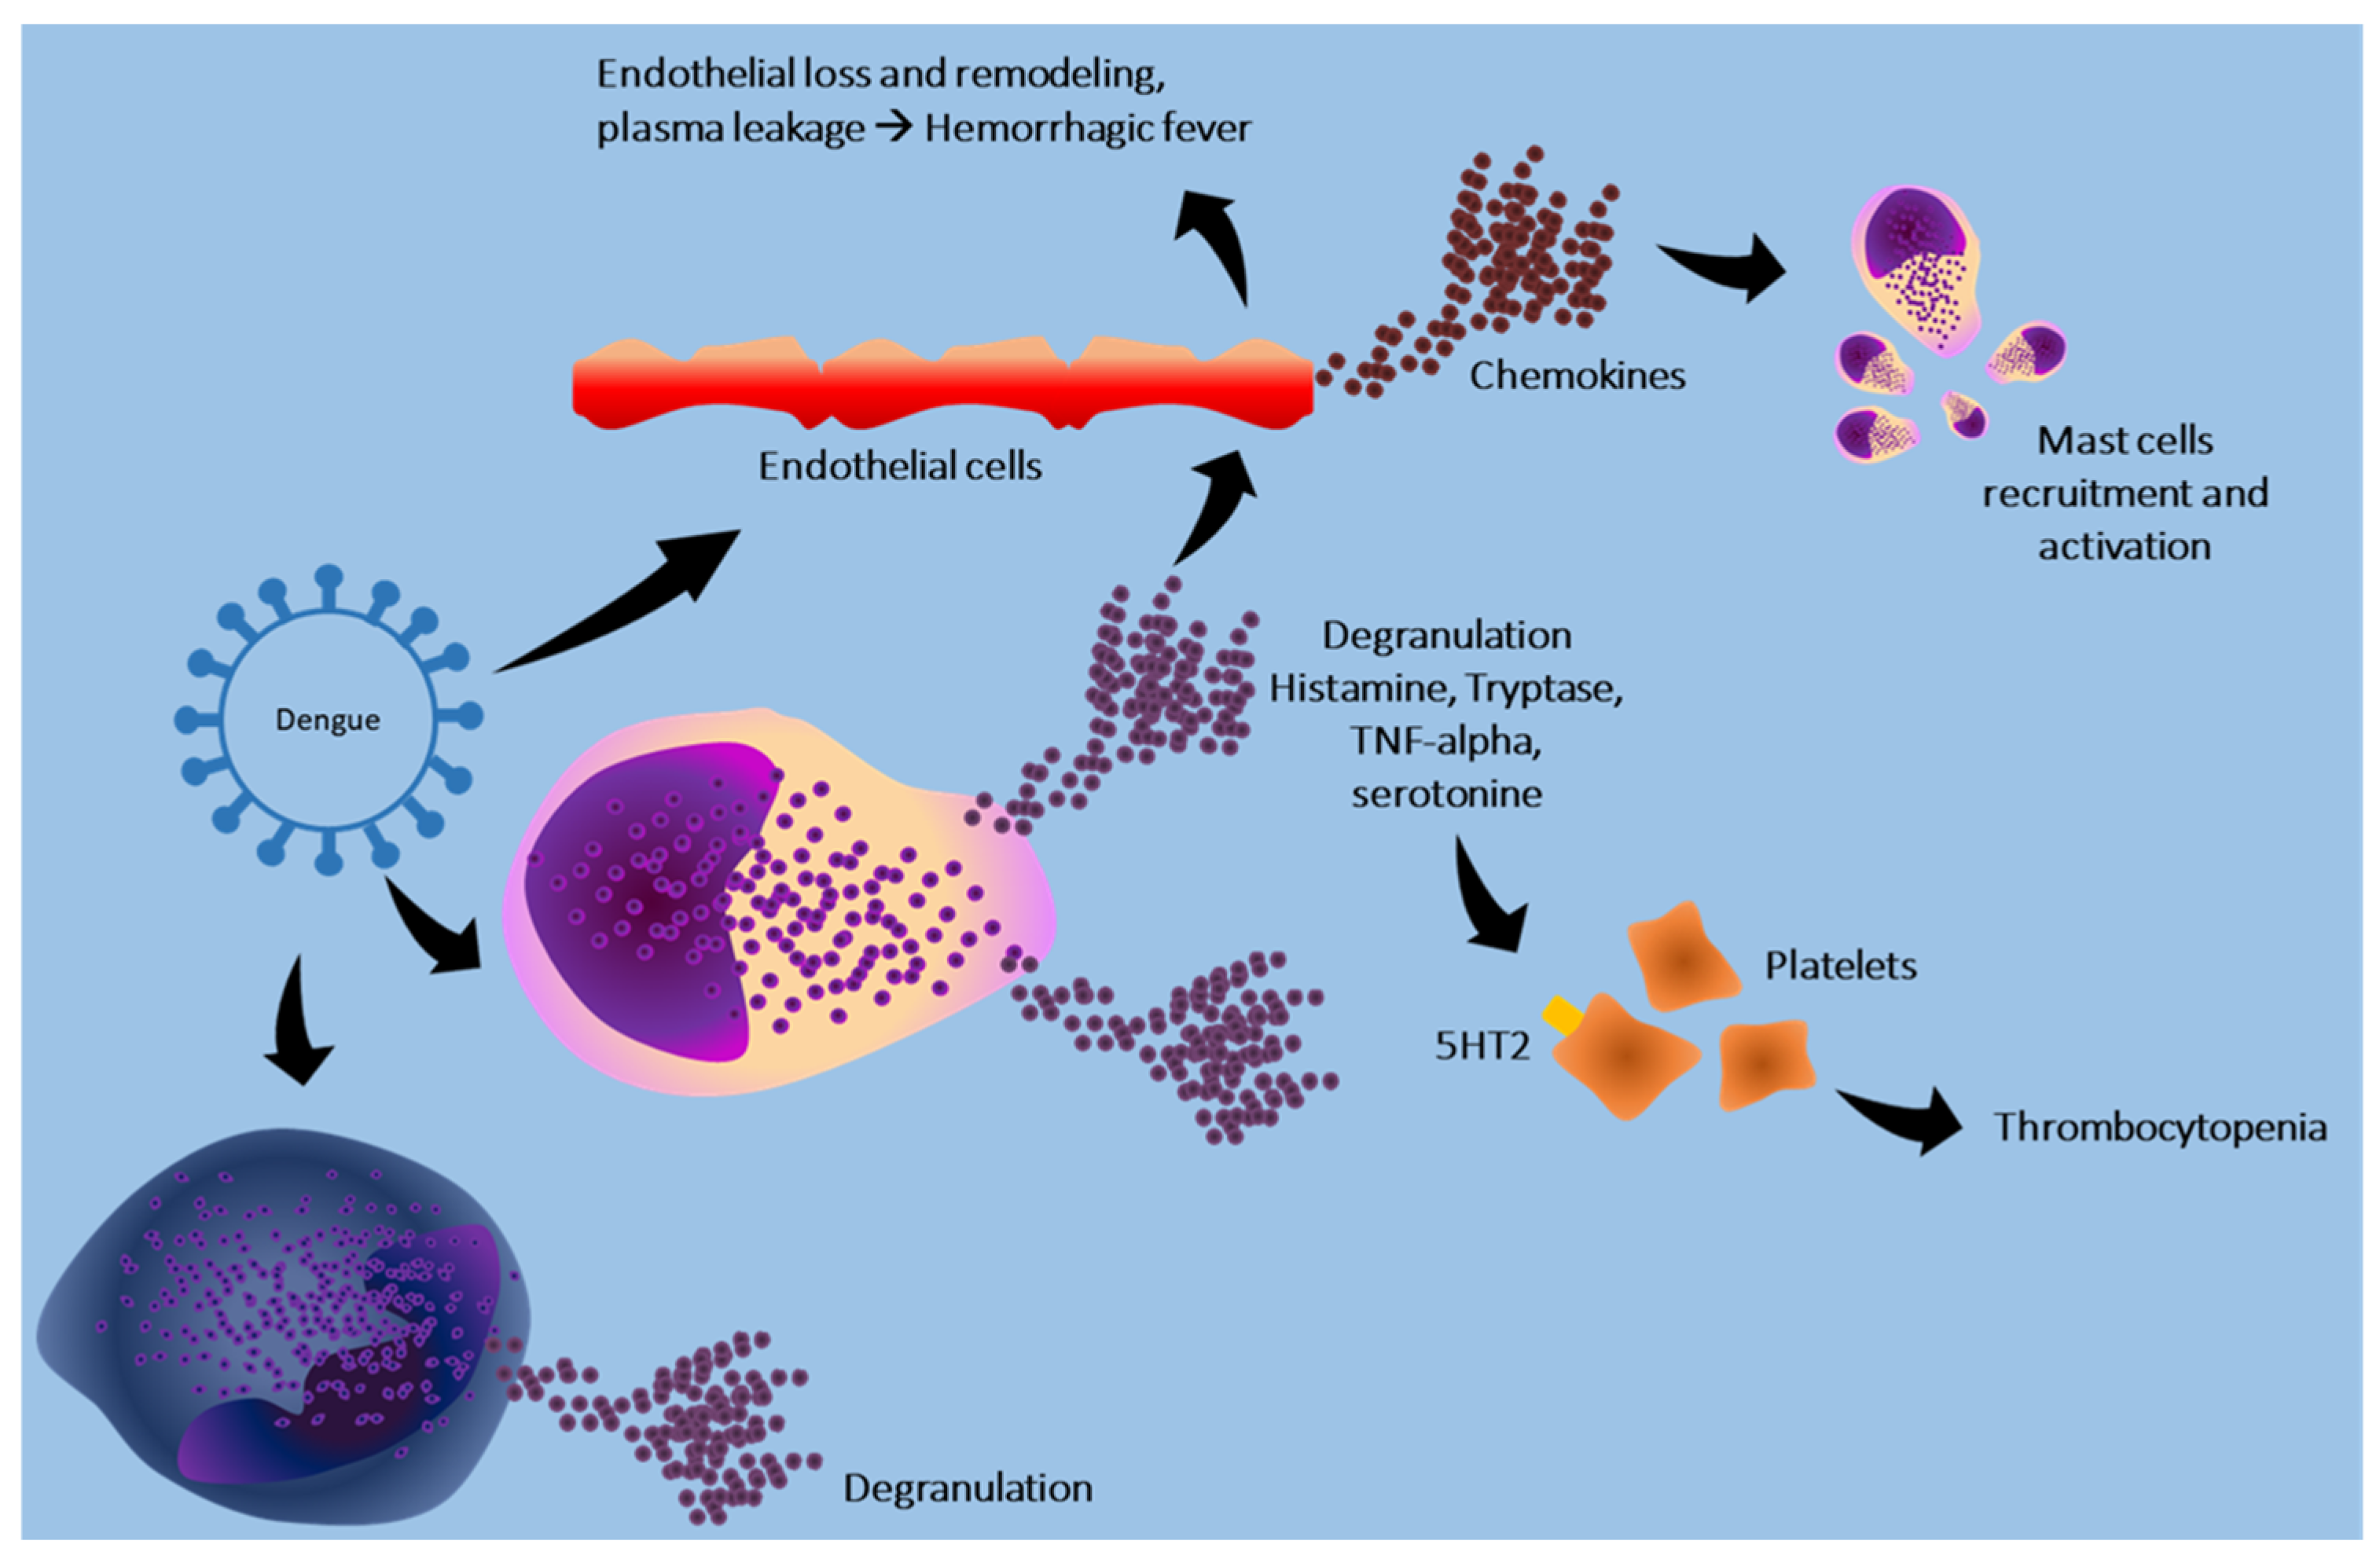
The mechanisms through which the dengue virus interacts with these cells are shown in Figure 4.
Figure 4.
Dengue virus stimulates endothelial cells to release chemokines that attract and activate mast cells. The virus stimulates these cells and, through the release of histamine, tryptase, and TNF-alpha, promotes endothelial damage. Furthermore, the release of serotonin by mast cells determines the activation of platelets, mediated by the 5HT2 receptor, promoting splenic sequestration of platelets and thrombocytopenia. The virus also promotes basophil degranulation.
Table 4 summarizes the work on the role of mast cells and basophiles in the infection.
Table 4.
Role of mast cells and basophils in dengue infection.
4. Discussion
Mast cells and basophils are cells of the innate immune system implicated in the adaptive Th2 response and appear to play a role in many viral infections [88,89]. This research has shed new light on the involvement of these cells in SARS-CoV-2 infection.
Mast cells are active in COVID-19 infection, particularly in determining lung damage, by producing proinflammatory cytokines [1]. New data have supported these results after the review mentioned above [13]. In particular, it has been seen how the spike glycoprotein of SARS-CoV-2 can induce mast cell degranulation.
Other authors have shown how changes in gene expression during infection can be useful to evaluate the prognosis of patients with SARS-CoV-2 infection.
As we previously reported [1], basophils are important both in the acute phase of the disease and in remission. In the acute phase, particularly in the most aggressive forms, a reduction in the number of basophils and the expression of CRTH2 is observed, with a significant increase in PD-L1. In advanced stages of the disease, basophils increase in number and help the humoral and cellular immune response by producing IL-4. More recent studies have also demonstrated the importance of basophils stimulated by IL-3 during infection. These cells produce large amounts of IL-13, which would be implicated in reducing inflammation and stimulating antibody production [19].
Many retrospective studies have focused on the possibility of using different laboratory indices as markers of disease or disease severity or even as indicators of risk of serious disease. However, the results regarding the role of basophils as indicators are conflicting in the literature and therefore further studies are required for them to be used for this purpose [21,22,23,24,25].
On the contrary, the use of machine learning for the creation of diagnostic and prognostic algorithms of disease from which a relevant role of basophils emerges is interesting [27,28,29,30,31].
This review shows how mast cells’ role also seems relevant to the immune response to influenza viruses. Several authors have recently studied the topic and there is a strong correlation between influenza A viruses and mast cells. Mast cells are mainly involved in lung damage that presents itself in the most severe forms of infection.
The virus promotes the release of inflammatory mediators, such as histamine, tryptase, and IFN-gamma, the latter being responsible for the apoptosis of respiratory epithelial cells and lung damage in the most severe forms of the disease. The identified pathways involved are RIG-I/MAVS and TRL-3.
In vivo studies on experimental animals of disease that have been effectively pharmacologically treated with molecules that act on the mastocyte support these data [40,41].
Several authors have evaluated the gene expression of these cells during infection compared to the cells of healthy subjects, discovering how the gene expression was profoundly different between infected and healthy cells and between mast cells infected with other subtypes of IAV.
While studies on mast cells are numerous, recent studies on the role of basophils in the pathogenesis of IAV are few.
These mainly concern the role of histamine and other inflammation mediators released by the basophils stimulated by the virus through the activity of neuroaminidase and haemagglutinin [46]. Also interesting is the protective role of the carbohydrates that would saturate the same receptors stimulated by the virus [47].
The possibility of using basophils as a prognostic indicator of illness has recently been assessed. Indeed, low basophil counts could be associated with the most severe forms of the disease [49].
Although the global impact of HIV is relevant, the scientific interest in the role of cells of innate immunity in the pathogenesis of the disease seems to have reduced in recent years.
In fact, until 2016, the interest of the scientific community towards mast cells and basophils was significantly greater than in recent years. Until then the study of the role of these cells in the infection were mainly aimed at their ability to transfer the virus to the CD4+ T cells [52]. Indeed, mast cells and basophils can release the virus in the circle and represents an endogenous source [58].
Several authors have also shown that HIV can induce the liberation of inflammation mediators through interaction with IgE linked to the membrane receptors present on basophils and mast cells. These results explain why these subjects are more sensitive to the development of allergic reactions to drugs.
Human lung mast cells, responsible for lung damage in immunocompromised patients, express FCεRI and is the interaction between IgE of VH3-family and the gp120 superantigene expressed by the virus that causes the release of proinflammatory mediators, angiogenetic and lymphangiogenetic factors by these cells, exacerbating the damage [62].
Mast cells play an active role in immune surveillance against the dengue virus, through the release of proinflammatory mediators, chemokine and the recruitment of NK cells.
Mast cells exercise their action through the secretion of TNF-alpha, CCL4 and 5, IFN and the recruitment of T lymphocytes, monocytes and NK cells. In response to the infection, mast cells together with basophils also produce other chemokines such as Vipers and Mip-1 with the ability to encourage the recruitment of the effector T cells [76]. Several mediators issued by these cells act together to determine the endothelial damage in the most serious forms of dengue [85].
5. Conclusions
Knowing the mechanisms behind the high contagiousness of viral infectious pathologies is essential to finding new ways to treat them. The role of innate immunity cells is often underestimated, but this knowledge could be valuable in facilitating the diagnostic–therapeutic process. Our analysis showed that mast cells and basophils play crucial roles in developing viral diseases, as we described. The mediators released by the degranulation of these cells following viral stimulation are implicated in inflammatory processes and could be a potential therapeutic target for preventing severe forms or complications related to the disease. The count of these cells associated with other clinical or laboratory indices could be useful for obtaining prognostic scores and the prognostic value could be more precise with input from ML algorithms. While mast cell studies are varied, those on basophils are limited, especially in studying HIV, IAVs, and the dengue virus, and further insights are needed. In the future, understanding these mechanisms better could lead to the development of innovative therapies and sensitive diagnostic tools that could help reduce the mortality linked to these pathologies.
Author Contributions
Conceptualization, L.G., S.S., C.A., S.G. and P.L.M.; methodology, L.G., S.S., C.A., S.G. and P.L.M.; writing—original draft preparation, L.G., S.S. and C.A.; writing—review and editing, L.G., S.G. and P.L.M.; supervision, S.G. and P.L.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Murdaca, G.; Di Gioacchino, M.; Greco, M.; Borro, M.; Paladin, F.; Petrarca, C.; Gangemi, S. Basophils and Mast Cells in COVID-19 Pathogenesis. Cells 2021, 10, 2754. [Google Scholar] [CrossRef] [Scilit]
- Theoharides, T.C. Potential Association of Mast Cells with Coronavirus Disease 2019. Ann. Allergy Asthma Immunol. 2021, 126, 217–218. [Google Scholar] [CrossRef] [Scilit]
- Marshall, J.S.; Portales-Cervantes, L.; Leong, E. Mast Cell Responses to Viruses and Pathogen Products. Int. J. Mol. Sci. 2019, 20, 4241. [Google Scholar] [CrossRef] [Scilit]
- Zhang, H.; Sun, Y.; Wang, Y.; Yazici, D.; Azkur, D.; Ogulur, I.; Azkur, A.K.; Yang, Z.; Chen, X.; Zhang, A.; et al. Recent Developments in the Immunopathology of COVID-19. Allergy 2023, 78, 369–388. [Google Scholar] [CrossRef] [Scilit]
- Conti, P.; Caraffa, A.; Tetè, G.; Gallenga, C.E.; Ross, R.; Kritas, S.K.; Frydas, I.; Younes, A.; Di Emidio, P.; Ronconi, G. Mast Cells Activated by SARS-CoV-2 Release Histamine Which Increases IL-1 Levels Causing Cytokine Storm and Inflammatory Reaction in COVID-19. J. Biol. Regul. Homeost. Agents 2020, 34, 1629–1632. [Google Scholar]
- Zhou, Z.; Ren, L.; Zhang, L.; Zhong, J.; Xiao, Y.; Jia, Z.; Guo, L.; Yang, J.; Wang, C.; Jiang, S.; et al. Heightened Innate Immune Responses in the Respiratory Tract of COVID-19 Patients. Cell Host Microbe 2020, 27, 883–890.e2. [Google Scholar] [CrossRef] [Scilit]
- Del Valle, D.M.; Kim-Schulze, S.; Huang, H.H.; Beckmann, N.D.; Nirenberg, S.; Wang, B.; Lavin, Y.; Swartz, T.H.; Madduri, D.; Stock, A.; et al. An Inflammatory Cytokine Signature Predicts COVID-19 Severity and Survival. Nat. Med. 2020, 26, 1636–1643. [Google Scholar] [CrossRef] [Scilit]
- Huang, C.; Wang, Y.; Li, X.; Ren, L.; Zhao, J.; Hu, Y.; Zhang, L.; Fan, G.; Xu, J.; Gu, X.; et al. Clinical Features of Patients Infected with 2019 Novel Coronavirus in Wuhan, China. Lancet 2020, 395, 497–506. [Google Scholar] [CrossRef] [Scilit]
- Zhou, F.; Yu, T.; Du, R.; Fan, G.; Liu, Y.; Liu, Z.; Xiang, J.; Wang, Y.; Song, B.; Gu, X.; et al. Clinical Course and Risk Factors for Mortality of Adult Inpatients with COVID-19 in Wuhan, China: A Retrospective Cohort Study. Lancet 2020, 395, 1054–1062. [Google Scholar] [CrossRef] [Scilit]
- Herold, T.; Jurinovic, V.; Arnreich, C.; Lipworth, B.J.; Hellmuth, J.C.; von Bergwelt-Baildon, M.; Klein, M.; Weinberger, T. Elevated Levels of IL-6 and CRP Predict the Need for Mechanical Ventilation in COVID-19. J. Allergy Clin. Immunol. 2020, 146, 128–136.e4. [Google Scholar] [CrossRef] [Scilit]
- Theoharides, T.C.; Conti, P. COVID-19 and Multisystem Inflammatory Syndrome, or Is It Mast Cell Activation Syndrome? J. Biol. Regul. Homeost. Agents 2020, 34, 1633–1636. [Google Scholar]
- Li, X.; Zhang, C.; Bao, Z. Mast Cell Activation May Contribute to Adverse Health Transitions in COVID-19 Patients with Frailty. Emerg. Microbes Infect. 2023, 12, 2251589. [Google Scholar] [CrossRef] [Scilit]
- Tan, J.Y.J.; Anderson, D.E.; Rathore, A.P.S.; O’Neill, A.; Mantri, C.K.; Saron, W.A.A.; Lee, C.Q.E.; Cui, C.W.; Kang, A.E.Z.; Foo, R.; et al. Mast Cell Activation in Lungs during SARS-CoV-2 Infection Associated with Lung Pathology and Severe COVID-19. J. Clin. Investig. 2023, 133, e149834. [Google Scholar] [CrossRef] [Scilit]
- Gebremeskel, S.; Schanin, J.; Coyle, K.M.; Butuci, M.; Luu, T.; Brock, E.C.; Xu, A.; Wong, A.; Leung, J.; Korver, W.; et al. Mast Cell and Eosinophil Activation Are Associated With COVID-19 and TLR-Mediated Viral Inflammation: Implications for an Anti-Siglec-8 Antibody. Front. Immunol. 2021, 12, 650331. [Google Scholar] [CrossRef] [Scilit]
- Cao, J.B.; Zhu, S.T.; Huang, X.S.; Wang, X.Y.; Wu, M.L.; Li, X.; Liu, F.L.; Chen, L.; Zheng, Y.T.; Wang, J.H. Mast Cell Degranulation-Triggered by SARS-CoV-2 Induces Tracheal-Bronchial Epithelial Inflammation and Injury. Virol. Sin. 2024, 39, 309–318. [Google Scholar] [CrossRef] [Scilit]
- MacCann, R.; Leon, A.A.G.; Gonzalez, G.; Carr, M.J.; Feeney, E.R.; Yousif, O.; Cotter, A.G.; de Barra, E.; Sadlier, C.; Doran, P.; et al. Dysregulated Early Transcriptional Signatures Linked to Mast Cell and Interferon Responses Are Implicated in COVID-19 Severity. Front. Immunol. 2023, 14, 1166574. [Google Scholar] [CrossRef] [Scilit]
- Wu, M.L.; Liu, F.L.; Sun, J.; Li, X.; He, X.Y.; Zheng, H.Y.; Zhou, Y.H.; Yan, Q.; Chen, L.; Yu, G.Y.; et al. SARS-CoV-2-Triggered Mast Cell Rapid Degranulation Induces Alveolar Epithelial Inflammation and Lung Injury. Signal Transduct. Target. Ther. 2021, 6, 428. [Google Scholar] [CrossRef] [Scilit]
- Liu, S.; Suzuki, Y.; Takemasa, E.; Watanabe, R.; Mogi, M. Mast Cells Promote Viral Entry of SARS-CoV-2 via Formation of Chymase/Spike Protein Complex. Eur. J. Pharmacol. 2022, 930, 175169. [Google Scholar] [CrossRef] [Scilit]
- Bonam, S.R.; Chauvin, C.; Levillayer, L.; Mathew, M.J.; Sakuntabhai, A.; Bayry, J. SARS-CoV-2 Induces Cytokine Responses in Human Basophils. Front. Immunol. 2022, 13, 838448. [Google Scholar] [CrossRef] [Scilit]
- Degenfeld-Schonburg, L.; Sadovnik, I.; Smiljkovic, D.; Peter, B.; Stefanzl, G.; Gstoettner, C.; Jaksch, P.; Hoetzenecker, K.; Aigner, C.; Radtke, C.; et al. Coronavirus Receptor Expression Profiles in Human Mast Cells, Basophils, and Eosinophils. Cells 2024, 13, 173. [Google Scholar] [CrossRef] [Scilit]
- Liu, J.; Gong, S.; Lv, J.; Wang, G.; Guo, Y.; Gao, D.; Zhang, D.; Ma, S.; Luo, H.; Yang, H.; et al. Clinical Features and Blood Indicators for Severity and Prognosis in COVID-19 Patients. Clin. Lab. 2023, 69, 742–748. [Google Scholar] [CrossRef] [Scilit]
- Lin, Y.; Yang, Y.; Xiang, N.; Wang, L.; Zheng, T.; Zhuo, X.; Shi, R.; Su, X.; Liu, Y.; Liao, G.; et al. Characterization and Trajectories of Hematological Parameters Prior to Severe COVID-19 Based on a Large-Scale Prospective Health Checkup Cohort in Western China: A Longitudinal Study of 13-Year Follow-Up. BMC Med. 2024, 22, 105. [Google Scholar] [CrossRef] [Scilit]
- Binsaleh, N.K.; Eltayeb, R.; Sherwani, S.; Almishaal, A.A.; Hindi, E.; Qanash, H.; Bazaid, A.; Alharbi, A.O.; Bazaid, M.; Altamimi, S.A. Comparison of Hematological Parameters Between Survivors and Non-Survivors COVID-19 Patients in Saudi Arabia. Int. J. Gen. Med. 2023, 16, 3955–3962. [Google Scholar] [CrossRef] [Scilit]
- Ben, S.; Gao, F.; Xu, Z.; Zhang, R.; Zhang, X.; Wang, N.; Zhang, M.; Hou, L. The Role of Hematological Parameters in Asymptomatic and Non-Severe Cases of Omicron Variant Infection. Virol. J. 2024, 21, 143. [Google Scholar] [CrossRef] [Scilit]
- Saeed, J.R.; Lal, A. Impact of Severity of Covid-19 on Haematological Parameters in Patients Reporting to Saidu Group of Teaching Hospitals, Swat. J. Ayub Med. Coll. Abbottabad 2023, 35, 80–83. [Google Scholar] [CrossRef] [Scilit]
- Danieli, M.G.; Brunetto, S.; Gammeri, L.; Palmeri, D.; Claudi, I.; Shoenfeld, Y.; Gangemi, S. Machine Learning Application in Autoimmune Diseases: State of Art and Future Prospectives. Autoimmun. Rev. 2024, 23, 103496. [Google Scholar] [CrossRef] [Scilit]
- Fu, Y.; Zhong, W.; Liu, T.; Li, J.; Xiao, K.; Ma, X.; Xie, L.; Jiang, J.; Zhou, H.; Liu, R.; et al. Early Prediction Model for Critical Illness of Hospitalized COVID-19 Patients Based on Machine Learning Techniques. Front. Public Health 2022, 10, 880999. [Google Scholar] [CrossRef] [Scilit]
- Chadaga, K.; Prabhu, S.; Sampathila, N.; Chadaga, R.; Umakanth, S.; Bhat, D.; GS, S.K. Explainable Artificial Intelligence Approaches for COVID-19 Prognosis Prediction Using Clinical Markers. Sci. Rep. 2024, 14, 1783. [Google Scholar] [CrossRef] [Scilit]
- de Souza, A.A.; de Almeida, D.C.; Barcelos, T.S.; Bortoletto, R.C.; Munoz, R.; Waldman, H.; Goes, M.A.; Silva, L.A. Simple Hemogram to Support the Decision-Making of COVID-19 Diagnosis Using Clusters Analysis with Self-Organizing Maps Neural Network. Soft Comput. 2023, 27, 3295–3306. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Li, X.; Xu, J.; Zhou, Q. A Complete Blood Count-Based Multivariate Model for Predicting the Recovery of Patients with Moderate COVID-19: A Retrospective Study. Sci. Rep. 2022, 12, 18262. [Google Scholar] [CrossRef] [Scilit]
- Baik, S.M.; Hong, K.S.; Park, D.J. Application and Utility of Boosting Machine Learning Model Based on Laboratory Test in the Differential Diagnosis of Non-COVID-19 Pneumonia and COVID-19. Clin. Biochem. 2023, 118, 110584. [Google Scholar] [CrossRef] [Scilit]
- Peteranderl, C.; Herold, S.; Schmoldt, C. Human Influenza Virus Infections. Semin. Respir. Crit. Care Med. 2016, 37, 487–500. [Google Scholar] [CrossRef] [Scilit]
- Abdelrahman, Z.; Li, M.; Wang, X. Comparative Review of SARS-CoV-2, SARS-CoV, MERS-CoV, and Influenza A Respiratory Viruses. Front. Immunol. 2020, 11, 552909. [Google Scholar] [CrossRef] [Scilit]
- Ng, K.; Raheem, J.; St Laurent, C.D.; Marcet, C.T.; Vliagoftis, H.; Befus, A.D.; Moon, T.C. Responses of Human Mast Cells and Epithelial Cells Following Exposure to Influenza A Virus. Antivir. Res. 2019, 171, 104566. [Google Scholar] [CrossRef] [Scilit]
- Hu, Y.; Jin, Y.; Han, D.; Zhang, G.; Cao, S.; Xie, J.; Xue, J.; Li, Y.; Meng, D.; Fan, X.; et al. Mast Cell-Induced Lung Injury in Mice Infected with H5N1 Influenza Virus. J. Virol. 2012, 86, 3347–3356. [Google Scholar] [CrossRef] [Scilit]
- Graham, A.C.; Hilmer, K.M.; Zickovich, J.M.; Obar, J.J. Inflammatory Response of Mast Cells during Influenza A Virus Infection Is Mediated by Active Infection and RIG-I Signaling. J. Immunol. 2013, 190, 4676–4684. [Google Scholar] [CrossRef] [Scilit]
- Meng, D.; Huo, C.; Wang, M.; Xiao, J.; Liu, B.; Wei, T.; Dong, H.; Zhang, G.; Hu, Y.; Sun, L. Influenza A Viruses Replicate Productively in Mouse Mastocytoma Cells (P815) and Trigger Pro-Inflammatory Cytokine and Chemokine Production through TLR3 Signaling Pathway. Front. Microbiol. 2017, 7, 2130. [Google Scholar] [CrossRef] [Scilit]
- Liu, B.; Meng, D.; Wei, T.; Zhang, S.; Hu, Y.; Wang, M. Apoptosis and Pro-Inflammatory Cytokine Response of Mast Cells Induced by Influenza A Viruses. PLoS ONE 2014, 9, e100109. [Google Scholar] [CrossRef] [Scilit]
- Desheva, Y.; Mamontov, A.; Petkova, N.; Karev, V.; Nazarov, P. Mast Cell Degranulation and Histamine Release during A/H5N1 Influenza Infection in Influenza-Sensitized Mice. Life Sci. 2020, 258, 118230. [Google Scholar] [CrossRef] [Scilit]
- Han, D.; Wei, T.; Zhang, S.; Wang, M.; Tian, H.; Cheng, J.; Xiao, J.; Hu, Y.; Chen, M. The Therapeutic Effects of Sodium Cromoglycate against Influenza A Virus H5N1 in Mice. Influenza Other Respir. Viruses 2016, 10, 57–66. [Google Scholar] [CrossRef] [Scilit]
- Huo, C.; Tang, Y.; Li, X.; Han, D.; Gu, Q.; Su, R.; Liu, Y.; Reiter, R.J.; Liu, G.; Hu, Y.; et al. Melatonin Alleviates Lung Injury in H1N1-Infected Mice by Mast Cell Inactivation and Cytokine Storm Suppression. PLoS Pathog. 2023, 19, e1011406. [Google Scholar] [CrossRef] [Scilit]
- Huo, C.; Wu, H.; Xiao, J.; Meng, D.; Zou, S.; Wang, M.; Qi, P.; Tian, H.; Hu, Y. Genomic and Bioinformatic Characterization of Mouse Mast Cells (P815) upon Different Influenza A Virus (H1N1, H5N1, and H7N2) Infections. Front. Genet. 2019, 10, 461843. [Google Scholar] [CrossRef] [Scilit]
- Wu, H.; Zhang, S.; Huo, C.; Zou, S.; Lian, Z.; Hu, Y. ITRAQ-Based Proteomic and Bioinformatic Characterization of Human Mast Cells upon Infection by the Influenza A Virus Strains H1N1 and H5N1. FEBS Lett. 2019, 593, 2612–2627. [Google Scholar] [CrossRef] [Scilit]
- Tang, Y.; Wu, H.; Huo, C.; Zou, S.; Hu, Y.; Yang, H. Transcriptomic Profiling of Mouse Mast Cells upon Pathogenic Avian H5N1 and Pandemic H1N1 Influenza a Virus Infection. Viruses 2022, 14, 292. [Google Scholar] [CrossRef] [Scilit]
- Clementsen, P.; Jensen, C.B.; Hannoun, C.; Søborg, M.; Norn, S. Influenza A Virus Potentiates Basophil Histamine Release Caused by Endotoxin-Induced Complement Activation. Examination of Normal Individuals and Patients with Intrinsic Asthma. Allergy 1988, 43, 93–99. [Google Scholar] [CrossRef] [Scilit]
- Clementsen, P.; Douglas, A.R.; Skehel, J.J.; Hannoun, C.; Bach-Mortensen, N.; Norn, S. Influenza A Virus Enhances IgE-Mediated Histamine Release from Human Basophil Leukocytes. Examination of the Effect of Viral Neuraminidase and Haemagglutinin. Agents Actions 1989, 27, 58–61. [Google Scholar] [CrossRef] [Scilit]
- Clementsen, P.; Norn, S.; Kristensen, K.S.; Hannoun, C. Influenza A Virus Enhances Basophil Histamine Release and the Enhancement Is Abolished by Carbohydrates. Allergy 1990, 45, 471–476. [Google Scholar] [CrossRef] [Scilit]
- Huftel, M.A.; Swensen, C.A.; Borcherding, W.R.; Dick, E.C.; Hong, R.; Kita, H.; Gleich, G.J.; Busse, W.W. The Effect of T-Cell Depletion on Enhanced Basophil Histamine Release after In Vitro Incubation with Live Influenza A Virus. Am. J. Respir. Cell Mol. Biol. 2012, 7, 434–440. [Google Scholar] [CrossRef] [Scilit]
- Wang, F.; Bian, S.; Zhou, W.; Liu, S.; Shu, Y.; Chen, Y. Causal Relationship between Blood Traits and Severe Influenza A(H1N1)Pdm09 Infection in East Asian: A Mendelian Randomization Study. J. Med. Virol. 2024, 96, e29736. [Google Scholar] [CrossRef] [Scilit]
- Sharp, P.M.; Hahn, B.H. Origins of HIV and the AIDS Pandemic. Cold Spring Harb. Perspect. Med. 2011, 1, a006841. [Google Scholar] [CrossRef] [Scilit]
- Hemelaar, J. The Origin and Diversity of the HIV-1 Pandemic. Trends Mol. Med. 2012, 18, 182–192. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; Varricchi, G.; Loffredo, S.; Galdiero, M.R.; Rivellese, F.; De Paulis, A. Are Basophils and Mast Cells Masters in HIV Infection? Int. Arch. Allergy Immunol. 2017, 171, 158–165. [Google Scholar]
- Obeagu, E.I.; Obeagu, G.U.; Akinleye, C.A. Unveiling the Enigmatic Roles of Basophils in HIV Infection: A Narrative Review. Medicine 2024, 103, e40384. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; Florio, G.; Triggiani, M.; Petraroli, A.; De Paulis, A. Mechanisms of IgE Elevation in HIV-1 Infection. Crit. Rev. Immunol. 2000, 20, 477–496. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; Florio, G.; Petraroli, A.; Triggiani, M.; De Paulis, A. Role of Human FcepsilonRI+ Cells in HIV-1 Infection. Immunol. Rev. 2001, 179, 128–138. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; Florio, G.; Petraroli, A.; De Paulis, A. Dysregulation of the IgE/FcϵRI Network in HIV-1 Infection. J. Allergy Clin. Immunol. 2001, 107, 22–30. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; De Paulis, A.; Florio, G.; Petraroli, A.; Rossi, F.W.; Triggiani, M. Are Mast Cells MASTers in HIV-1 Infection? Int. Arch. Allergy Immunol. 2001, 125, 89–95. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Li, X.; Wadley, R.; Reddel, S.W.; Qi, J.C.; Archis, C.; Collins, A.; Clark, E.; Cooley, M.; Kouts, S.; et al. Mast Cells/Basophils in the Peripheral Blood of Allergic Individuals Who Are HIV-1 Susceptible Due to Their Surface Expression of CD4 and the Chemokine Receptors CCR3, CCR5, and CXCR4. Blood 2001, 97, 3484–3490. [Google Scholar] [CrossRef] [Scilit]
- Rossi, F.W.; Prevete, N.; Rivellese, F.; Lobasso, A.; Napolitano, F.; Granata, F.; Selleri, C.; De Paulis, A. HIV-1 Nef Promotes Migration and Chemokine Synthesis of Human Basophils and Mast Cells through the Interaction with CXCR4. Clin. Mol. Allergy 2016, 14, 15. [Google Scholar] [CrossRef] [Scilit]
- Sundstrom, J.B.; Hair, G.A.; Ansari, A.A.; Secor, W.E.; Gilfillan, A.M.; Metcalfe, D.D.; Kirshenbaum, A.S. IgE-FcepsilonRI Interactions Determine HIV Coreceptor Usage and Susceptibility to Infection during Ontogeny of Mast Cells. J. Immunol. 2009, 182, 6401–6409. [Google Scholar] [CrossRef] [Scilit]
- Song, S.T.; Wu, M.L.; Zhang, H.J.; Su, X.; Wang, J.H. Mast Cell Activation Triggered by Retrovirus Promotes Acute Viral Infection. Front. Microbiol. 2022, 13, 798660. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; Rossi, F.W.; Pecoraro, A.; Pucino, V.; Criscuolo, G.; de Paulis, A.; Spadaro, G.; Marone, G.; Varricchi, G. HIV Gp120 Induces the Release of Proinflammatory, Angiogenic, and Lymphangiogenic Factors from Human Lung Mast Cells. Vaccines 2020, 8, 208. [Google Scholar] [CrossRef] [Scilit]
- Obeagu, E.I. Diagnostic and Prognostic Significance of Mast Cell Markers in HIV/AIDS: Current Insights and Future Directions. Medicine 2024, 103, E38117. [Google Scholar] [CrossRef] [Scilit]
- Rathore, A.P.S.; St John, A.L. Immune Responses to Dengue Virus in the Skin. Open Biol. 2018, 8, 180087. [Google Scholar] [CrossRef] [Scilit]
- Khanam, A.; Gutiérrez-Barbosa, H.; Lyke, K.E.; Chua, J.V. Immune-Mediated Pathogenesis in Dengue Virus Infection. Viruses 2022, 14, 2575. [Google Scholar] [CrossRef] [Scilit]
- Tuchinda, M.; Dhorranintra, B.; Tuchinda, P. Histamine Content in 24-Hour Urine in Patients with Dengue Haemorrhagic Fever. Southeast. Asian J. Trop. Med. Public Health 1977, 8, 80–83. [Google Scholar]
- Troupin, A.; Shirley, D.; Londono-Renteria, B.; Watson, A.M.; McHale, C.; Hall, A.; Hartstone-Rose, A.; Klimstra, W.B.; Gomez, G.; Colpitts, T.M. A Role for Human Skin Mast Cells in Dengue Virus Infection and Systemic Spread. J. Immunol. 2016, 197, 4382–4391. [Google Scholar] [CrossRef] [Scilit]
- Dalrymple, N.A.; Mackow, E.R. Endothelial Cells Elicit Immune-Enhancing Responses to Dengue Virus Infection. J. Virol. 2012, 86, 6408–6415. [Google Scholar] [CrossRef] [Scilit]
- John, A.L.S.; Rathore, A.P.S.; Yap, H.; Ng, M.L.; Metcalfe, D.D.; Vasudevan, S.G.; Abraham, S.N. Immune Surveillance by Mast Cells during Dengue Infection Promotes Natural Killer (NK) and NKT-Cell Recruitment and Viral Clearance. Proc. Natl. Acad. Sci. USA 2011, 108, 9190–9195. [Google Scholar] [CrossRef] [Scilit]
- Chu, Y.T.; Wan, S.W.; Anderson, R.; Lin, Y.S. Mast Cell–Macrophage Dynamics in Modulation of Dengue Virus Infection in Skin. Immunology 2015, 146, 163–172. [Google Scholar] [CrossRef] [Scilit]
- Brown, M.G.; McAlpine, S.M.; Huang, Y.Y.; Haidl, I.D.; Al-Afif, A.; Marshall, J.S.; Anderson, R. RNA Sensors Enable Human Mast Cell Anti-Viral Chemokine Production and IFN-Mediated Protection in Response to Antibody-Enhanced Dengue Virus Infection. PLoS ONE 2012, 7, e34055. [Google Scholar] [CrossRef] [Scilit]
- Morrison, J.; Rathore, A.P.S.; Mantri, C.K.; Aman, S.A.B.; Nishida, A.; St.John, A.L. Transcriptional Profiling Confirms the Therapeutic Effects of Mast Cell Stabilization in a Dengue Disease Model. J. Virol. 2017, 91, e00617-17. [Google Scholar] [CrossRef] [Scilit]
- Mantri, C.K.; Soundarajan, G.; Saron, W.A.A.; Rathore, A.P.S.; Alonso, S.; John, A.L.S. Maternal Immunity and Vaccination Influence Disease Severity in Progeny in a Novel Mast Cell-Deficient Mouse Model of Severe Dengue. Viruses 2021, 13, 900. [Google Scholar] [CrossRef] [Scilit]
- Bozza, F.A.; Cruz, O.G.; Zagne, S.M.O.; Azeredo, E.L.; Nogueira, R.M.R.; Assis, E.F.; Bozza, P.T.; Kubelka, C.F. Multiplex Cytokine Profile from Dengue Patients: MIP-1beta and IFN-Gamma as Predictive Factors for Severity. BMC Infect. Dis. 2008, 8, 86. [Google Scholar] [CrossRef] [Scilit]
- Pérez, A.B.; García, G.; Sierra, B.; Alvarez, M.; Vázquez, S.; Cabrera, M.V.; Rodríguez, R.; Rosario, D.; Martínez, E.; Denny, T.; et al. IL-10 Levels in Dengue Patients: Some Findings from the Exceptional Epidemiological Conditions in Cuba. J. Med. Virol. 2004, 73, 230–234. [Google Scholar] [CrossRef] [Scilit]
- King, C.A.; Anderson, R.; Marshall, J.S. Dengue Virus Selectively Induces Human Mast Cell Chemokine Production. J. Virol. 2002, 76, 8408–8419. [Google Scholar] [CrossRef] [Scilit]
- Brown, M.G.; Hermann, L.L.; Issekutz, A.C.; Marshall, J.S.; Rowter, D.; Al-Afif, A.; Anderson, R. Dengue Virus Infection of Mast Cells Triggers Endothelial Cell Activation. J. Virol. 2011, 85, 1145–1150. [Google Scholar] [CrossRef] [Scilit]
- Chu, Y.T.; Wan, S.W.; Chang, Y.C.; Lee, C.K.; Wu-Hsieh, B.A.; Anderson, R.; Lin, Y.S. Antibodies against Nonstructural Protein 1 Protect Mice from Dengue Virus-Induced Mast Cell Activation. Lab. Investig. 2017, 97, 602–614. [Google Scholar] [CrossRef] [Scilit]
- Tissera, H.; Rathore, A.P.S.; Leong, W.Y.; Pike, B.L.; Warkentien, T.E.; Farouk, F.S.; Syenina, A.; Ooi, E.E.; Gubler, D.J.; Wilder-Smith, A.; et al. Chymase Level Is a Predictive Biomarker of Dengue Hemorrhagic Fever in Pediatric and Adult Patients. J. Infect. Dis. 2017, 216, 1112–1121. [Google Scholar] [CrossRef] [Scilit]
- Sahu, A.K.; Aggarwal, P.; Ekka, M.; Nayer, J.; Bhoi, S.; Kumar, A.; Luthra, K. Assessing the Serum Chymase Level as an Early Predictor of Dengue Severity. J. Med. Virol. 2021, 93, 3330–3337. [Google Scholar] [CrossRef] [Scilit]
- St John, A.L.; Rathore, A.P.S.; Raghavan, B.; Ng, M.L.; Abraham, S.N. Contributions of Mast Cells and Vasoactive Products, Leukotrienes and Chymase, to Dengue Virus-Induced Vascular Leakage. Elife 2013, 2013, e00481. [Google Scholar] [CrossRef] [Scilit]
- Rathore, A.P.S.; Mantri, C.K.; Aman, S.A.B.; Syenina, A.; Ooi, J.; Jagaraj, C.J.; Goh, C.C.; Tissera, H.; Wilder-Smith, A.; Ng, L.G.; et al. Dengue Virus–Elicited Tryptase Induces Endothelial Permeability and Shock. J. Clin. Investig. 2019, 129, 4180–4193. [Google Scholar] [CrossRef] [Scilit]
- Vasquez Velasquez, C.; Roman, A.D.; Lan, N.T.P.; Huy, N.T.; Mercado, E.S.; Espino, F.E.; Perez, M.L.M.; Huong, V.T.Q.; Thuy, T.T.; Tham, V.D.; et al. Alpha Tryptase Allele of Tryptase 1 (TPSAB1) Gene Associated with Dengue Hemorrhagic Fever (DHF) and Dengue Shock Syndrome (DSS) in Vietnam and Philippines. Hum. Immunol. 2015, 76, 318–323. [Google Scholar] [CrossRef] [Scilit]
- Masri, M.F.B.; Mantri, C.K.; Rathore, A.P.S.; St. John, A.L. Peripheral Serotonin Causes Dengue Virus–Induced Thrombocytopenia through 5HT2 Receptors. Blood 2019, 133, 2325–2337. [Google Scholar] [CrossRef] [Scilit]
- King, C.A.; Marshall, J.S.; Alshurafa, H.; Anderson, R. Release of Vasoactive Cytokines by Antibody-Enhanced Dengue Virus Infection of a Human Mast Cell/Basophil Line. J. Virol. 2000, 74, 7146–7150. [Google Scholar] [CrossRef] [Scilit]
- Brown, M.G.; King, C.A.; Sherren, C.; Marshall, J.S.; Anderson, R. A Dominant Role for FcγRII in Antibody-Enhanced Dengue Virus Infection of Human Mast Cells and Associated CCL5 Release. J. Leukoc. Biol. 2006, 80, 1242–1250. [Google Scholar] [CrossRef] [Scilit]
- Jeewandara, C.; Gomes, L.; Udari, S.; Paranavitane, S.A.; Shyamali, N.L.A.; Ogg, G.S.; Malavige, G.N. Secretory Phospholipase A2 in the Pathogenesis of Acute Dengue Infection. Immun. Inflamm. Dis. 2016, 5, 7–15. [Google Scholar] [CrossRef] [Scilit]
- Wedemeyer, J.; Tsai, M.; Galli, S.J. Roles of Mast Cells and Basophils in Innate and Acquired Immunity. Curr. Opin. Immunol. 2000, 12, 624–631. [Google Scholar] [CrossRef] [Scilit]
- Marone, G.; Florio, G.; Petraroli, A.; Triggiani, M.; De Paulis, A. Human Mast Cells and Basophils in HIV-1 Infection. Trends Immunol. 2001, 22, 229–232. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).