


Simple Summary
Cervical dysplasia is one of the most common disorders of the female genital tract affecting millions of women worldwide. This systematic review of the literature of the last decade shows that significant progress has been made in its diagnosis and treatment. Based on >30 controlled clinical trials, specific and evidence-based recommendations can be formulated, such as for intravenous or intracervical lidocaine for pain reduction during colposcopically-directed cervical biopsies, but not topical lidocaine, music, or video colposcopy. Monsel’s solution might be used to control bleeding after cervical biopsies. The acetic acid test should be scored after 1 min and should be followed by Lugol’s iodine test for an optimal detection of dysplastic lesions. Loop electrical excision using standard instrumentation and techniques should be performed under local anesthesia and with direct colposcopic vision. Cryotherapy and thermoablation might be used in women with low-grade dysplasia, especially in women with HIV infection. Topical imiquimod remains an experimental procedure.
Abstract
Cervical dysplasia is a common precancerous lesion affecting 1% to 2% of women worldwide. Significant progress in the diagnosis and treatment of cervical dysplasia have been made in the last decade. We performed a systematic literature search of the databases PubMed and Cochrane Central Register of Controlled Trials to identify controlled clinical trials reporting on the efficacy and safety of diagnostic and therapeutic interventions for cervical dysplasia. Data were analyzed according to PRISMA guidelines. In total, 33 studies reporting on 5935 women were identified. We recommend intravenous or intracervical lidocaine for pain reduction during colposcopically-directed cervical biopsies but not topical lidocaine, music, or video colposcopy. Monsel’s solution might be used to control bleeding after cervical biopsies. The acetic acid test should be scored 1 min after the application of acetic acid and should be followed by Lugol’s iodine test for an optimal yield of LSIL/HSIL. LEEP/LLETZ remains the standard and techniques such as SWETZ, C-LETZ, and TCBEE are not superior. LEEP/LLETZ should be performed under local anesthesia and with direct colposcopic vision. Cryotherapy and thermoablation might be used in women with LSIL, especially in women with HIV infection, but LEEP/LLETZ remains the standard for HSIL. Topical imiquimod remains an experimental procedure. In conclusion, significant progress has been made in the last decade regarding both diagnostic interventions as well as therapeutic interventions for women with cervical dysplasia. Based on >30 controlled clinical trials, we were able to formulate specific and evidence-based recommendations.
1. Introduction
Cervical dysplasia is one of the most common disorders in gynecology. Specifically, precancerous lesions of the cervix such as low-grade squamous intraepithelial lesions (LSIL) and high-grade squamous intraepithelial lesions (HSIL) affect 1% to 3% of women taking part in national cervical cancer screening programs [1,2]. Cervical dysplasia is a virus-associated disorder and is caused in >95% of cases by an infection with high-risk subtypes of the Human Papilloma Virus (HPV), which ranks among the most common sexually transmitted infectious diseases worldwide [3]. Subsequent to the high incidence of cervical dysplasia, surgical interventions aimed at treating LSIL/HSIL before they develop into invasive cervical cancer are among the most common surgical interventions in Gynecology. For example, approximately half a million loop electrosurgical excision (LEEP) and large loop excision of the transformation zone (LLETZ) procedures are being performed in the United States each year [4]. Aside from the immediate consequences of cervical surgery such as pain, anxiety, and costs, LEEP/LLETZ also causes long-term adverse effects such as an increased risk of preterm delivery. Specifically, the height of the removed cone [5] and the presence of an HPV-related lesion alone, even without the execution of an excisional treatment [6], has been associated with a worsening of obstetric outcomes. In a systematic review of 32 studies, for example, Monti et al. found a significantly elevated risk of premature delivery, low birth weight, and premature rupture of membranes in women with a history of surgery for cervical dysplasia [7]. This statistically and clinically significant increase in obstetrical risks is directly correlated with the number and extent of cervical procedures such as LEEP and LLETZ [8]. Therefore, effective means for the management of cervical dysplasia are a major medical need for women worldwide. Evidence-based strategies for the diagnosis and treatment of cervical dysplasia are necessary to guarantee optimal outcomes and to avoid or minimize long-term sequelae, such as premature birth. In the last decade, numerous randomized controlled trials (RCTs) and non-randomized prospective controlled trials (PCTs) have been performed designed to refine the diagnosis of LSIL/HSIL with interventions such as colposcopy, acetic acid test, and Lugol’s iodine test. Likewise, numerous RCTs and PCTs have been performed aimed at improving the efficacy and safety of surgical interventions such as cryotherapy, LEEP, and LLETZ. In the present systematic review, we summarize all RCTs and PCTs assessing diagnostic and therapeutic interventions for cervical dysplasia published during the last decade. Based on the results of these studies, we comprehensively discuss the current evidence-based standard of care for the management of women with cervical dysplasia.
2. Materials and Methods
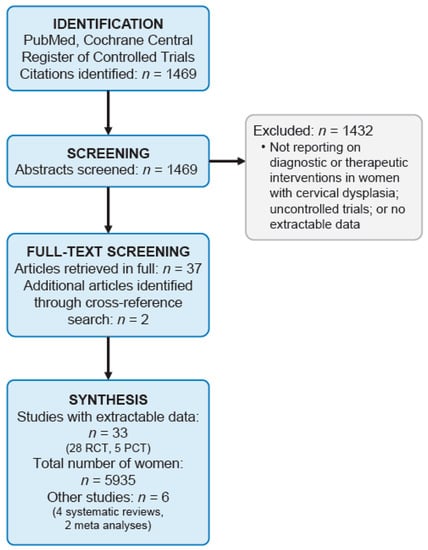
We performed a systematic literature search of the databases PubMed and Cochrane Central Register of Controlled Trials using the search terms ((“uterine cervical dysplasia”[MeSH Terms] OR (“uterine”[All Fields] AND “cervical”[All Fields] AND “dysplasia”[All Fields]) OR “uterine cervical dysplasia”[All Fields] OR (“cervical”[All Fields] AND “dysplasia”[All Fields]) OR “cervical dysplasia”[All Fields] OR “cervical intraepithelial neoplasia”[MeSH Terms] OR (“cervical”[All Fields] AND “intraepithelial”[All Fields] AND “neoplasia”[All Fields]) OR “cervical intraepithelial neoplasia”[All Fields] OR (“cervical”[All Fields] AND “dysplasia”[All Fields])) AND (“colposcopy”[MeSH Terms] OR “colposcopy”[All Fields] OR “colposcopies”[All Fields])) OR ((“conisation”[All Fields] OR “conization”[MeSH Terms] OR “conization”[All Fields] OR “conisations”[All Fields] OR “conizations”[All Fields] OR “conized”[All Fields]) AND (“random allocation”[MeSH Terms] OR (“random”[All Fields] AND “allocation”[All Fields]) OR “random allocation”[All Fields] OR “random”[All Fields] OR “randomization”[All Fields] OR “randomized”[All Fields] OR “randomisation”[All Fields] OR “randomisations”[All Fields] OR “randomise”[All Fields] OR “randomised”[All Fields] OR “randomising”[All Fields] OR “randomizations”[All Fields] OR “randomize”[All Fields] OR “randomizes”[All Fields] OR “randomizing”[All Fields] OR “randomness”[All Fields] OR “randoms”[All Fields])) (search date: 15 March 2022). The methodology followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) criteria [9]. The Population/Problem–Intervention/Exposure–Comparison–Outcome (PICO) question [10] defined to guide the selection of studies was as follows: What are the optimal diagnostic and therapeutic procedures for women with cervical dysplasia based on controlled trials with regard to diagnostic sensitivity and specificity, treatment efficacy, and side effects? Screening, eligibility, and data analysis were performed by two authors independently (JMH and CBT). Discrepancies were solved by consensus. Study investigators were not contacted to obtain further information. The literature search was restricted to controlled trials, i.e., RCTs and PCTs, defined as prospective cohort studies with upfront-defined inclusion/exclusion criteria and outcomes. Methodological quality was assessed in all studies using the Cochrane RoB 2.0 (randomized trials; [11]) or MINORS (non-randomized trials; [12]) tools. with the above-described search strategy, we identified 5076 citations. Therefore, the search was restricted to the last 10 y, i.e., published January 2012 or later. After screening all abstracts, appropriate citations, i.e., those reporting on diagnostic and therapeutic interventions in women with cervical dysplasia within a controlled trial setting, were selected. Studies not reporting individual patient data, uncontrolled trials, and studies containing no extractable clinical data were excluded. All citations were then retrieved in full and cross reference searching was performed in order to identify further studies. Figure 1 shows a flow diagram of the literature search algorithm. Data were extracted and analyzed in a descriptive manner. Meta-analysis was not performed due to the heterogeneity of studies. The protocol for this review has not been registered.
Figure 1.
Flow diagram of the literature search algorithm.
In order to identify ongoing clinical trials, we additionally searched the website of the National Institutes of Health clinical trials database (www.clinicaltrials.gov) using the search term “cervical dysplasia” (search date: 4 April 2022). We selected only studies assessing diagnostic and therapeutic interventions in women with proven or suspected cervical dysplasia. Studies evaluating screening strategies for cervical dysplasia were not included.
3. Results
In a systematic literature search using the search criteria as described above (search date: 15 March 2022), we identified 1469 citations. 1432 citations were excluded because they did not report on diagnostic and therapeutic interventions in women with cervical dysplasia within a controlled trial setting as defined for the purpose of this review. Using the remaining 37 citations, cross reference searching identified two further appropriate citations. Thus, in summary, 39 citations reporting on diagnostic and therapeutic interventions in women with cervical dysplasia within a controlled trial setting were included in this review [13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51]. Among them, we found 5 PCTs [13,14,15,16,17] and 28 RCTs [18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45], describing in summary 5935 patients. In addition, we found 6 systematic reviews and meta-analyses [46,47,48,49,50,51].
The clinical characteristics of the 33 studies reporting individual patient data are shown in Table 1 and Table 2. Specifically, the clinical characteristics of individual studies reporting on diagnostic procedures in women with cervical dysplasia are shown in Table 1, and those reporting on therapeutic procedures in women with cervical dysplasia are shown in Table 2. Table 3 shows the clinical characteristics of 27 ongoing studies assessing diagnostic and therapeutic interventions in women with cervical dysplasia listed within the National Institutes of Health clinical trials database (www.clinicaltrials.gov, search date: 4 April 2022).
Table 1.
Clinical characteristics of studies reporting on diagnostic procedures in women with cervical dysplasia.
Table 2.
Clinical characteristics of studies reporting on therapeutic procedures in women with cervical dysplasia.
Table 3.
Study characteristics of ongoing clinical trials listed at clinicaltrials.gov.
3.1. Diagnostic Studies in Women with Suspected or Proven Cervical Dysplasia
The clinical characteristics of individual studies reporting on diagnostic procedures in women with cervical dysplasia are shown in Table 1. We identified 12 studies. In total, 8 studies with 1390 participants were RCTs [18,19,20,21,22,23,24,25] and 4 studies with 893 participants were PCTs [13,14,15,16]. In 7 RCTs, interventions aimed at reducing pain during colposcopy and colposcopically-controlled cervical biopsies were evaluated [18,20,21,22,23,24,25]. In summary, these studies demonstrate that intravenous or intracervical lidocaine is efficacious for reducing pain [21,24,25] (this was not seen in one PCT [13]), whereas mixed results were reported for topical lidocaine spray on the cervix vs. placebo or forced coughing [18,23]. In addition, music as well as video colposcopy (with the patient watching the procedure) did not reduce pain during colposcopy [20,22]. One RCT looked at bleeding control after colposcopically-controlled biopsies by use of Monsel’s solution demonstrating that Monsel’s solution was efficacious in reducing blood loss and duration after biopsies [19]. Two PCTs evaluated the optimal use of the acetowhite acid test [14] and Lugol’s iodine test [16]. The best time to identify acetowhite lesions was 1 min after the application of acetic acid with fading of acetowhite lesions being common and time-dependent supporting a recommendation of not prolonging colposcopy beyond 3 min [14]. Lugol’s iodine showed moderate sensitivity and poor specificity, but it changed the clinical management in 5% of cases when used in addition to acetic acid [16]. Finally, one PCT found that 4 random cervical biopsies at the squamocolumnar junction resulted in an optimal yield of cervical intraepithelial neoplasia (CIN) 2+ lesions in women with a cytology of LSIL or Atypical Squamous Cells of Undetermined Significance (ASCUS) who had a normal colposcopic impression [15].
3.2. Therapeutic Studies in Women with Suspected or Proven Cervical Dysplasia
The clinical characteristics of individual studies reporting on therapeutic procedures in women with cervical dysplasia are shown in Table 2. We identified 20 RCTs with 3355 participants [26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45] and one PCT with 297 participants [17]. in total, 4 RCTs found that alternative electrosurgical techniques such as Straight Wire Excision of the Transformation Zone (SWETZ), Contour-Loop Excision of the Transformation Zone (C-LETZ), and True Cone Biopsy Electrode Excision (TCBEE) were comparable to the standard LEEP/LLETZ procedure with minimal differences regarding specimen fragmentation and endocervical resection margin status [26,27,28,31]. LEEP performed under direct colposcopic vision led to smaller cone sizes without compromising margin status [33], but video colposcopy did not have this benefit [44]. Spray coagulation was better than forced coagulation for intra-operative bleeding control [29] and a chitosan tampon effectively reduced post-operative bleeding episodes [37]. Patients preferred LEEP under local anesthesia over general anesthesia [38]. Cryotherapy as well as thermoablation were found to be safe and efficacious in women with LSIL, especially in women with HIV infection [30,32,36,39], but LLETZ was superior when treating HSIL [34]. Topical imiquimod was efficacious for the treatment of LSIL/HSIL but was less effective than surgery [40,45].
3.3. Methodological Assessment of Diagnostic and Therapeutic Studies in Women with Cervical Dysplasia
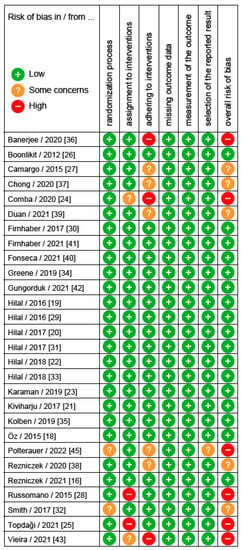
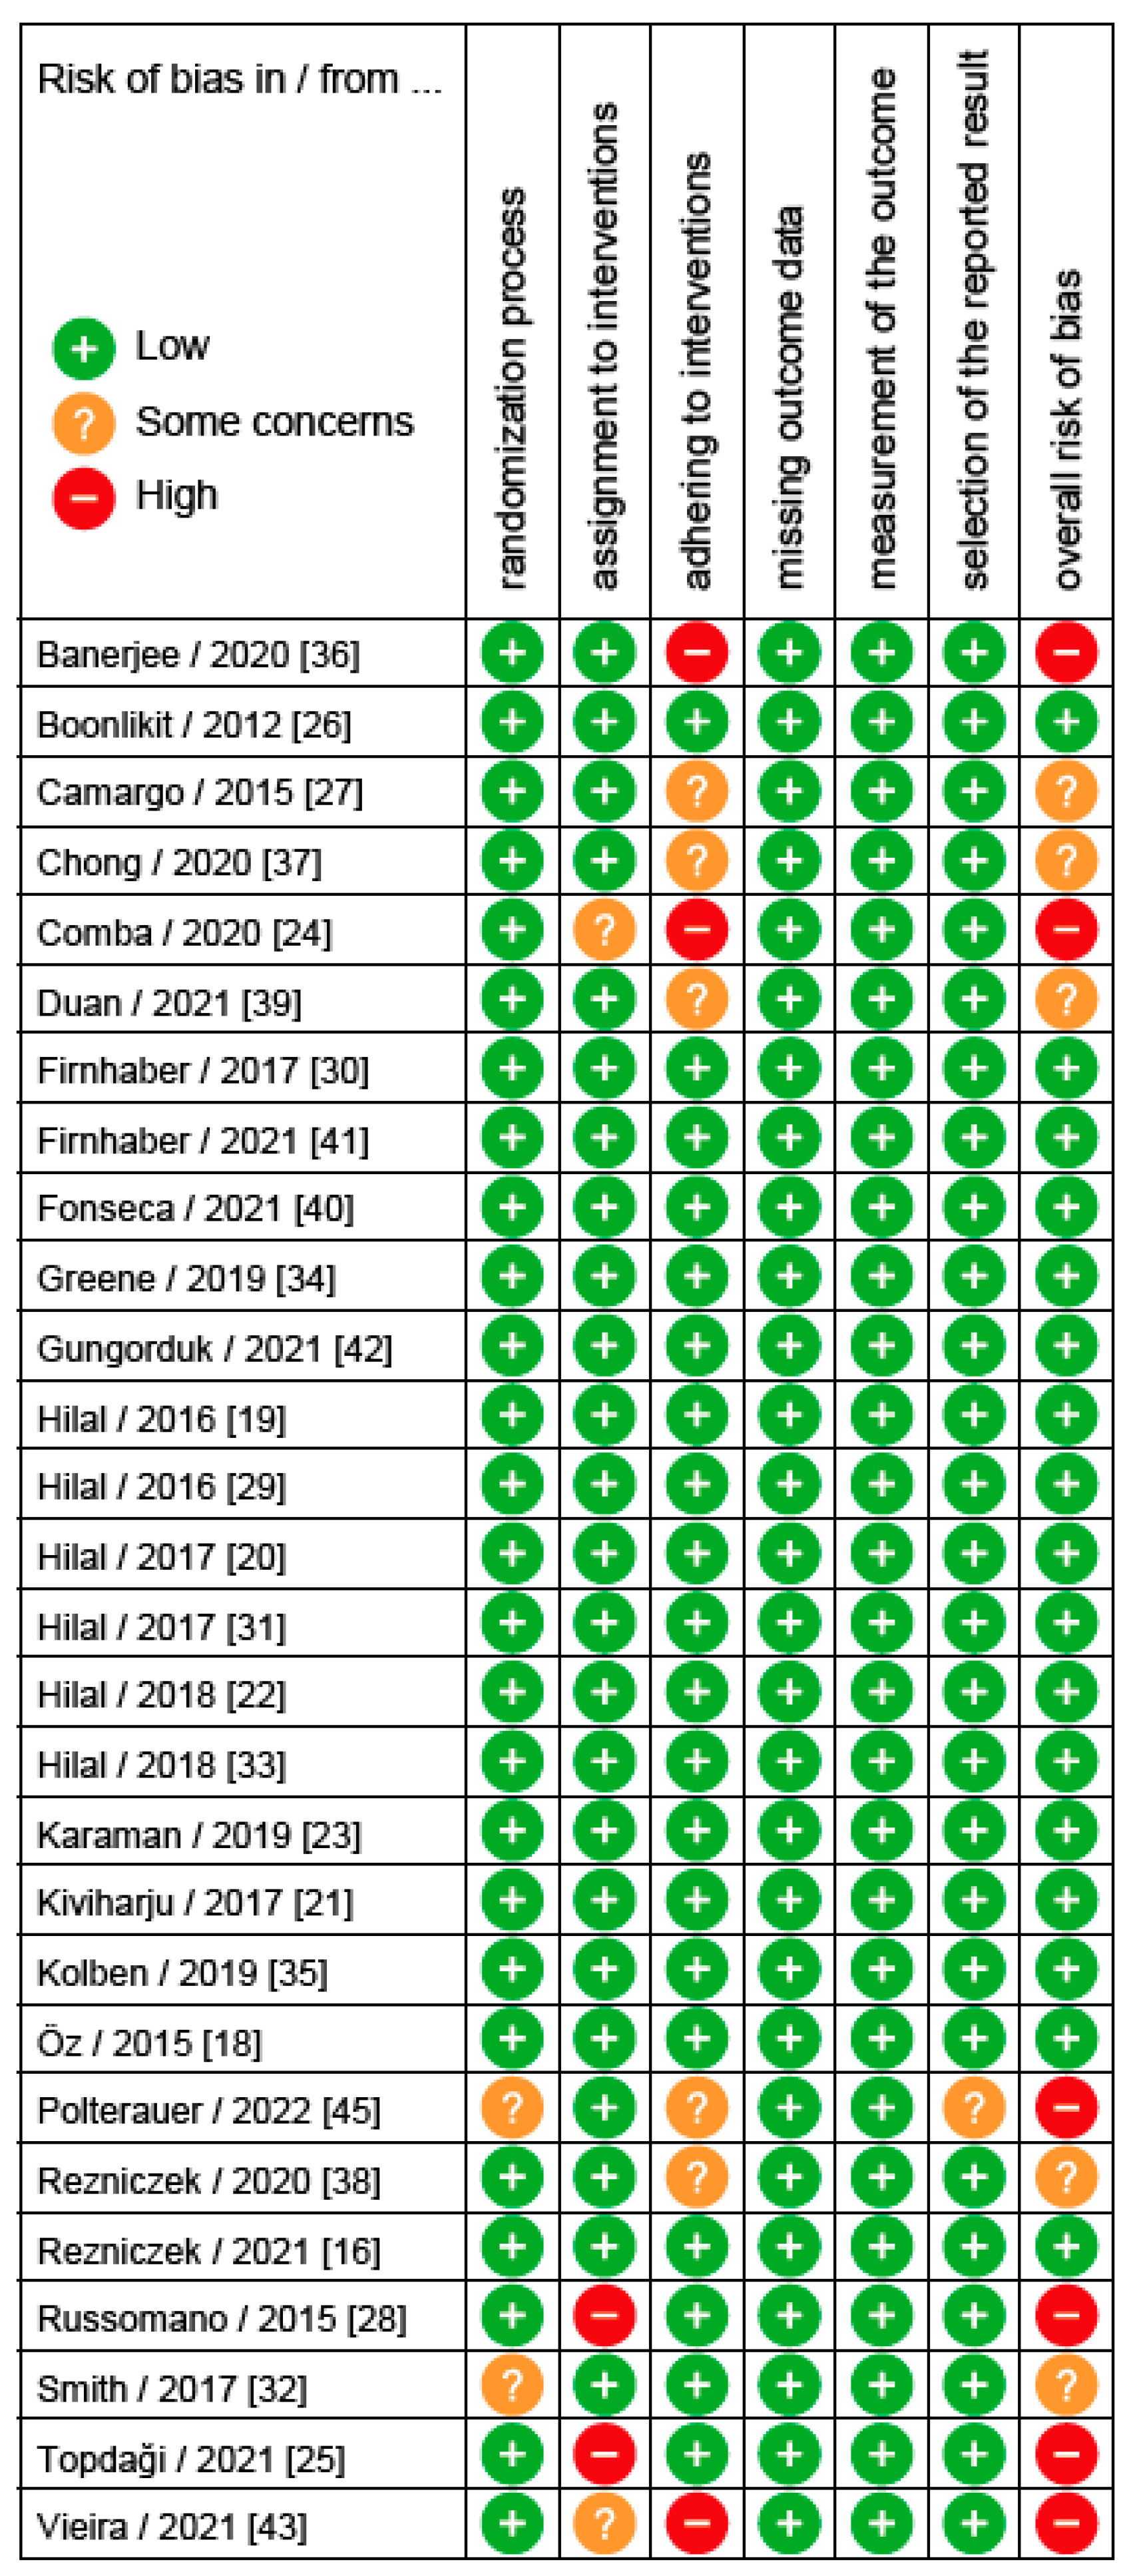
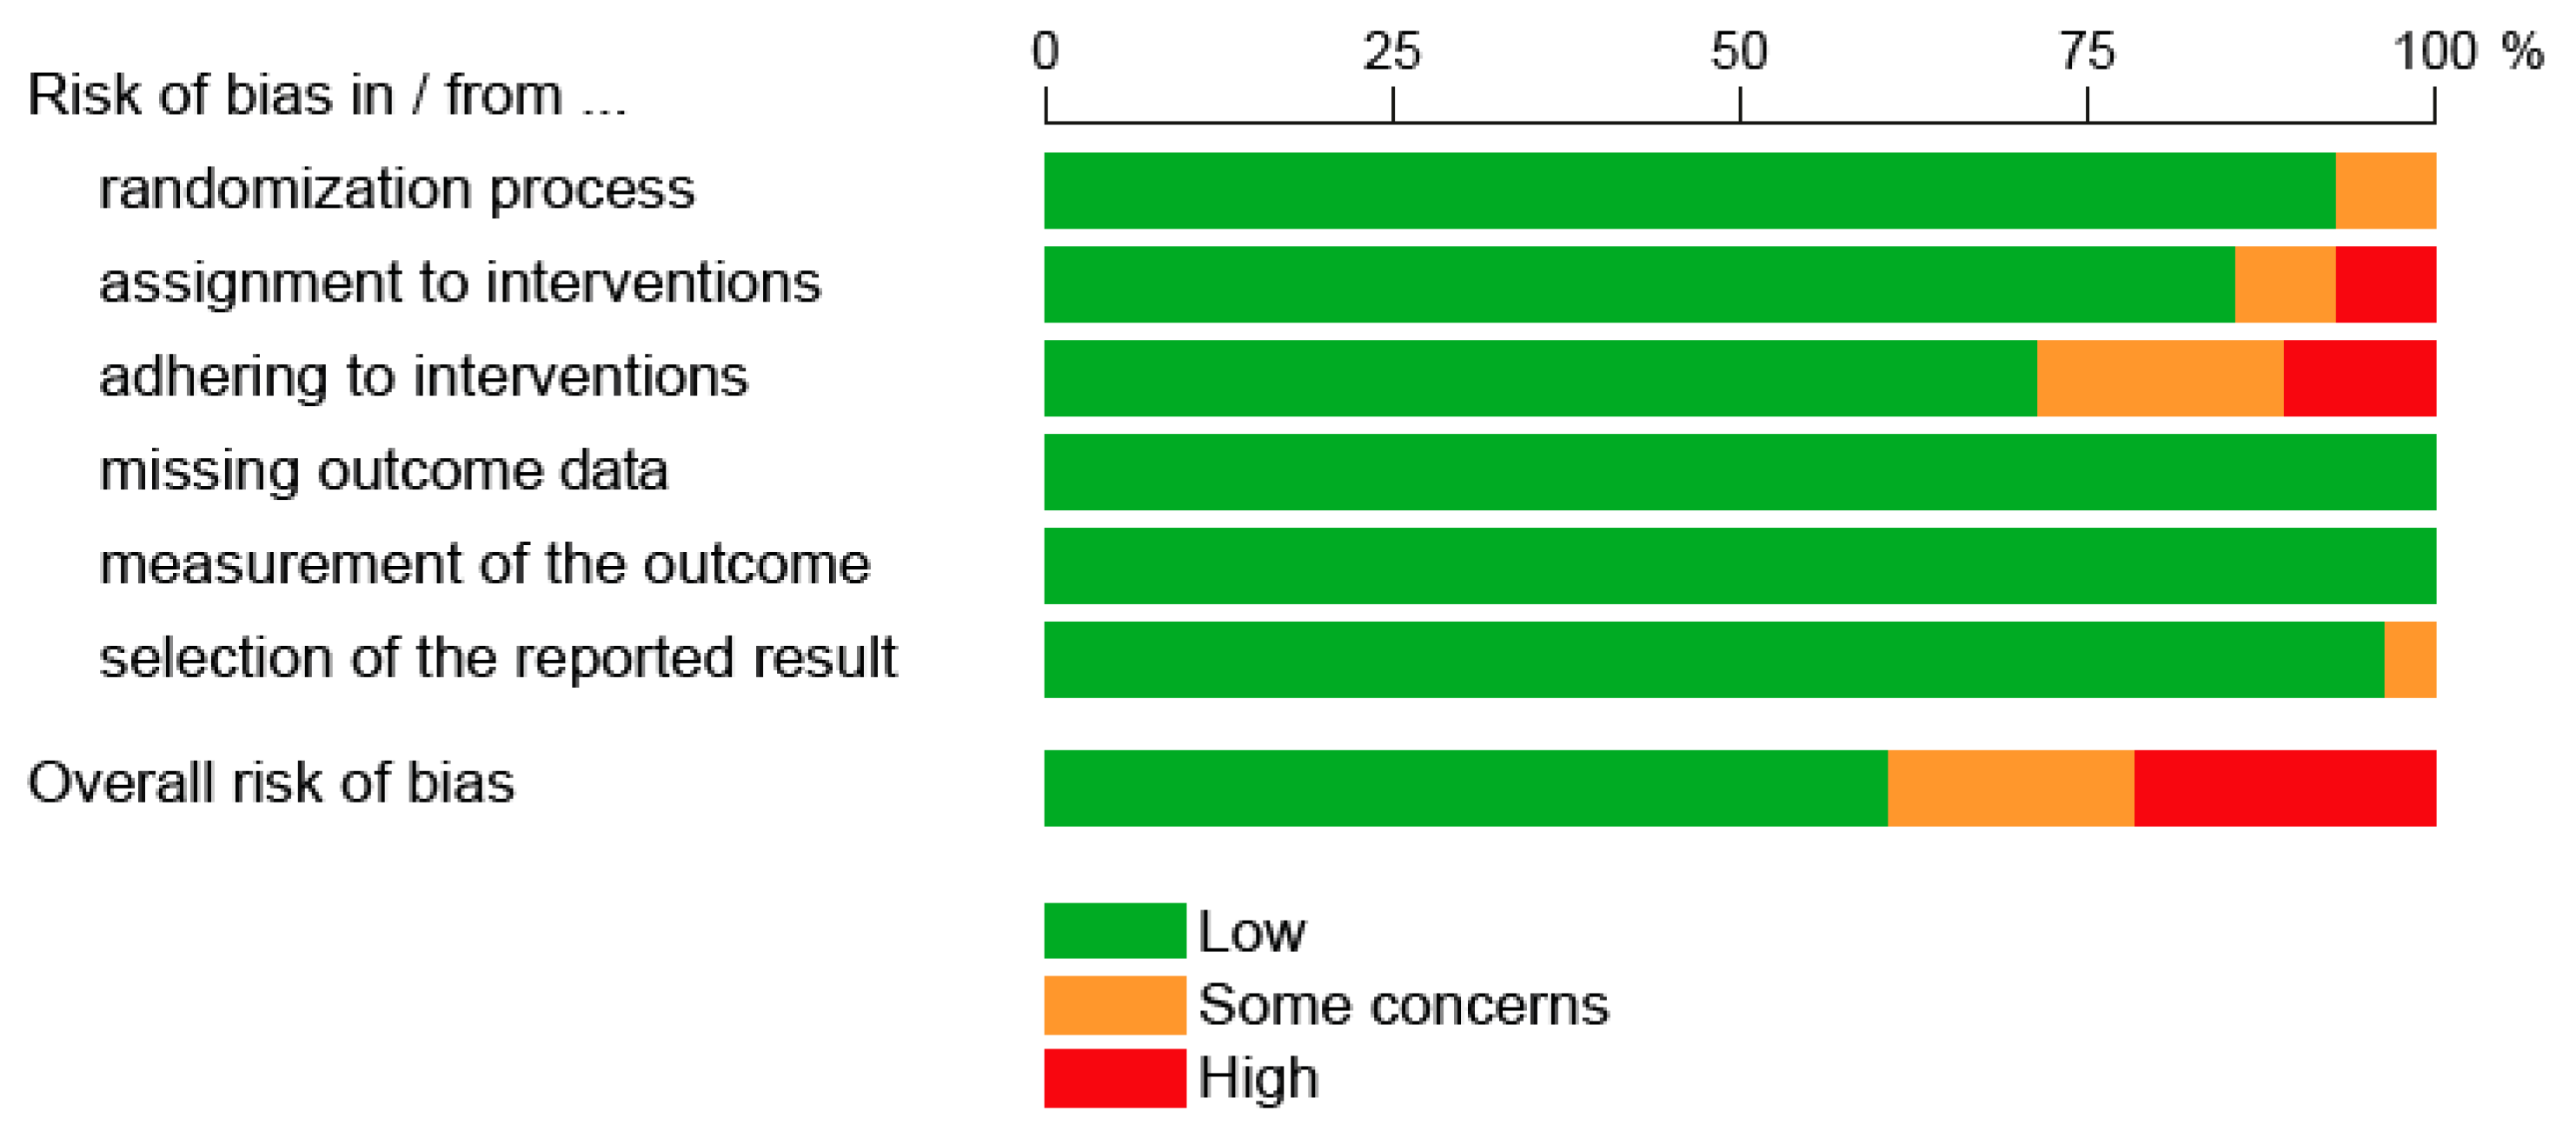
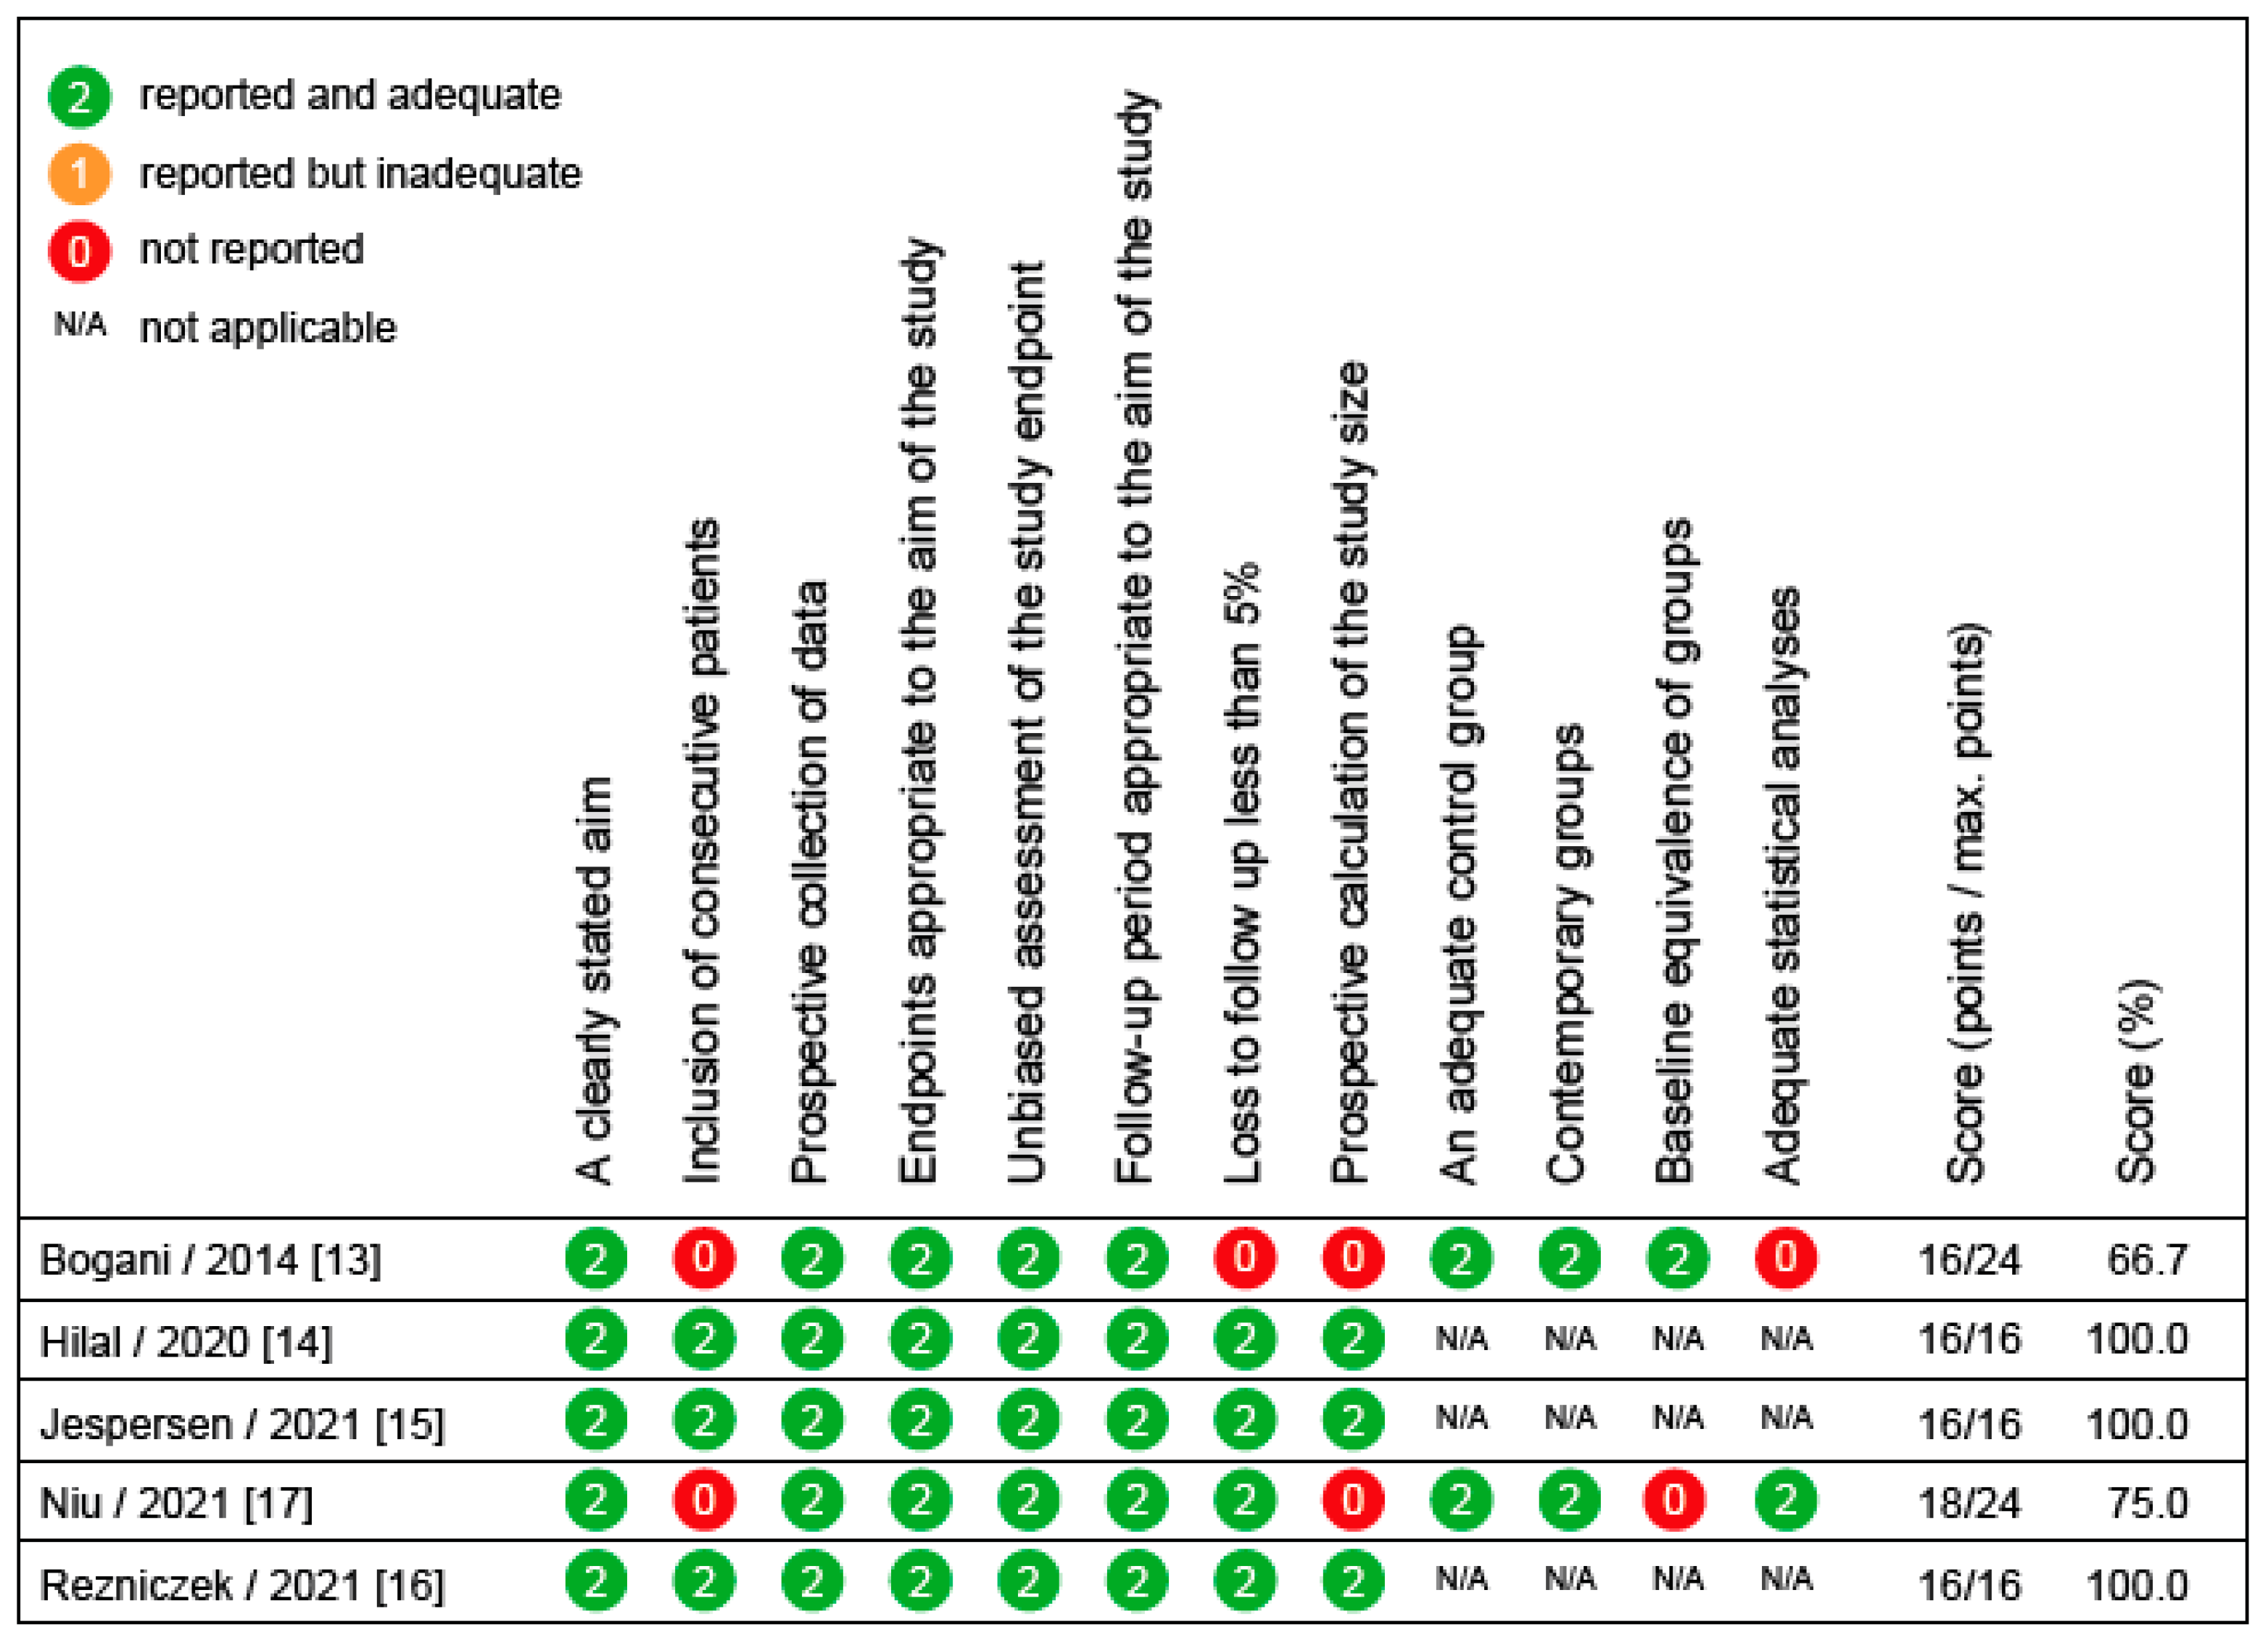
Figure 2 shows the methodological quality of all 21 RCTs. In 6/21 trials, there was a significant risk of bias [24,25,28,36,43,45], limiting the validity of the results. Figure 3 shows the overall and specific bias risks given as a percentage of all RCTs. This figure shows that assignment to and adherence to the study interventions were the main methodological problems causing a bad rating. In these cases, limiting the interpretation to the per protocol analyses might be useful. Figure 4 shows the methodological quality of the 5 diagnostic trials. In 2/5 trials, significant risks of bias were detected [13,17], limiting the validity of the results. Since both studies had multiple issues, the results of these studies must be interpreted with caution.
Figure 2.
Methodological quality summary (according to the Cochrane Risk of Bias 2 tool [11]): Review authors’ judgements about each methodological quality item for each included study reporting on a randomized controlled trial (n = 28).
Figure 3.
“Risk of bias” graph: Review authors’ judgements about each “Risk of bias” item presented as percentages across all included randomized controlled trials (n = 28). See Figure 2 for details.
Figure 4.
Methodological quality assessment and scores of prospective, non-randomized trials (n = 5), according to the revised methodological index for non-randomized studies (MINORS; [12]).
3.4. Systematic Reviews of Diagnostic or Therapeutic Interventions in Women with Cervical Dysplasia
We identified six systematic reviews and meta-analyses analyzing diagnostic or therapeutic interventions in women with cervical dysplasia [46,47,48,49,50,51]. Five of them analyzed therapeutic interventions. One systematic review compared different interventions to reduce blood loss during cervical surgery [46]. Two of the systematic reviews analyzed studies comparing cryotherapy and LEEP/LLETZ [48,50] and further two reviews analyzed photodynamic therapy, an experimental, non-invasive therapy of cervical dysplasia [49,51]. One systematic review looked at pain relief during colposcopy, the standard diagnostic intervention for women with suspected cervical dysplasia [47]. The specific details of the six systematic reviews are described below.
D’Alessandro et al. performed a meta-analysis of 4 trials with 1035 women with LSIL/HSIL and compared the efficacy of LEEP/LLETZ vs. cryotherapy [50]. Biopsy-proven LSIL/HSIL persistence after 6 m was the primary endpoint. LEEP/LLETZ was superior regarding the primary endpoint (relative risk [RR]: 0.87, 95% confidence interval [CI]: 0.76–0.99). The rate of biopsy-proven LSIL/HSIL after 12 m (secondary endpoint) also favored LEEP/LLETZ over cryotherapy (RR: 0.91, 95% CI: 0.84–0.99). Moreover, the superiority of LEEP/LLETZ was visible in the subgroups of women with HSIL only and HIV-positive women (RR: 0.89, 95% CI: 0.77–0.98 and RR: 0.88, 95% CI: 0.76–0.99, respectively). Complications did not differ between LEEP/LLETZ and cryotherapy.
Santesso et al. identified 167 randomized controlled trials and non-randomized controlled trials comparing three different types of surgery in women with LSIL/HSIL, i.e., LEEP/LLETZ, cold-knife conization, and cryotherapy [48]. They found that cold-knife conization was more effective compared to LEEP/LLETZ and cryotherapy but resulted in more short-term and long-term complications. Specifically, the rate of LSIL/HSIL recurrence 12 m after surgery was 5% for LEEP/LLETZ and cryotherapy compared to only 1.4% after cold-knife conization. On the other hand, there were fewer major bleeding episodes requiring hospital admission or blood transfusions after cryotherapy compared to cold-knife conization (RR 0.15; 95% CI 0.10–0.20) as well as fewer major infections (RR 0.17; 95% CI 0.07–0.43), fewer surgical complications (RR 0.11; 95% CI 0.03–0.38), and fewer episodes of minor bleeding (RR 0.03; 95% CI 0.02–0.06). Comparisons of cryotherapy and LEEP/LLETZ showed fewer infections (RR 0.12; 95% CI 0.06–0.28) and fewer episodes of minor bleeding (RR 0.46; 95% CI 0.37–0.56) after cryotherapy. The most important long-term complication after cervical surgery, premature birth, occurred most often after cold-knife conization (RR 3.41; 95% CI 2.38–4.88).
Pain relief during colposcopy was the focus of a systematic review and meta-analysis of 19 RCTs with 1720 probands by Gajjar et al. [47]. There was no difference in pain relief when using oral analgesics compared with placebo or no treatment (mean difference (MD) −3.51; 95% CI −10.03 to 3.01; 129 women), whereas the combination of an intracervical injection of a local anesthetic with a vasoconstrictor (e.g., lignocaine plus adrenaline or prilocaine plus felypressin) resulted in less pain (MD −23.73; 95% CI −37.53 to −9.93; 95 women).
Martin-Hirsch and Bryant analyzed RCTs aimed at assessing interventions to reduce blood loss during cervical surgery [46]. Twelve RCTs with 1520 probands were included in the meta-analysis. Vasopressin significantly reduced peri-operative bleeding (MD −100.80, 95% CI −129.48 to −72.12) and the risk of intra-operative bleeding (RR 0.39, 95% CI 0.27 to 0.56). Tranexamic acid also significantly reduced secondary bleeding episodes (RR 0.23, 95% CI 0.11 to 0.50) and post-operative blood loss (MD −55.60, 95% CI −94.91 to −16.29). Lastly, packing with Monsel’s solution reduced peri-operative blood loss (MD −22.00, 95% CI −23.09 to −20.91) and post-operative dysmenorrhea (RR 0.37, 95% CI 0.16 to 0.84) as well as unsatisfactory colposcopy (RR 0.43, 95% CI 0.30 to 0.63) and cervical stenosis (RR 0.35, 95% CI 0.25 to 0.49).
Zhang et al. analyzed the evidence regarding an alternative treatment to LEEP/LLETZ, namely photodynamic therapy, a non-invasive experimental local therapy of cervical dysplasia [49]. They included four RCTs with 433 probands. Compared with placebo, photodynamic therapy was safe and significantly increased the complete remission rate of LSIL/HSIL (odds ratio [OR] 2.51; 95% CI 1.23–5.12) as well as cervical HPV infection (OR 3.82; 95% CI 1.91–7.65). Specifically, the remission rates with photodynamic therapy were between 77% and 82%.
Unanyan et al. again analyzed the available evidence regarding photodynamic therapy 3 y later [51]. They identified six controlled trials and confirmed that photodynamic therapy was safe and more effective than placebo in the treatment of LSIL and HSIL and holds promise, particularly in young women, because it does not lead to obstetrical problems during subsequent pregnancies. However, no comparative trials vs. the standard therapy (LEEP/LLETZ) was identified.
3.5. Ongoing Studies
We searched the US government website clinicaltrials.gov to identify ongoing studies assessing diagnostic and therapeutic interventions in women with cervical dysplasia. Searching for “cervical dysplasia” resulted in 378 studies. Studies assessing cervical cancer screening strategies/interventions and those not evaluating diagnostic or therapeutic interventions on a patient-specific level were excluded (n = 351). We identified 27 studies matching the inclusion criteria. Study design and study characteristics are presented in Table 3. Eight currently ongoing studies look at the value of different surgical techniques, two studies at methods to improve the diagnosis of cervical dysplasia, 13 studies assess various experimental therapeutics, among them trichloracetic acid, curcumin, estradiol, and pembrolizumab. One study looks at the therapeutic effect of a licensed HPV vaccine and three studies prospectively assess spontaneous regression rates of LSIL/HSIL.
4. Discussion
Cervical dysplasia is one of the most common disorders of the female genital tract affecting millions of women worldwide. The World Health Organization (WHO) estimates that 1% to 2% of women worldwide develop HSIL every year [48]. The annual prevalence of HSIL among women living with the Human Immunodeficiency Virus (HIV) is even higher, at 10%. Therefore, evidence-based diagnostic and therapeutic interventions for LSIL/HSIL are an important worldwide medical need. In order to clarify what progress has been made in this field during the last decade, we systematically searched the literature between 2012 and 2021 and identified 39 high-quality controlled trials, RCTs, and PCTs, reporting on diagnostic and therapeutic interventions in women with cervical dysplasia [13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51]. Among them, we found 5 PCTs [13,14,15,16,17] and 28 RCTs [18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45], describing in summary 5935 patients. In addition, we found 6 systematic reviews and meta-analyses [46,47,48,49,50,51]. This amount of clinical trials demonstrates that significant progress in the diagnosis and treatment of LSIL/HSIL has been made during the last decade allowing us to outline up-to-date recommendations for an evidence-based diagnosis and treatment of affected women.
The diagnostic and therapeutic studies included in this review have variable methodological qualities. Therefore, we have addressed this and have graded the risk of bias of all 21 RCTs and 5 diagnostic trials. Of note, in a third of all trials, significant methodological limitations regarding patient selection, randomization process, and interpretation were identified. Thus, further confirmatory trials are necessary to assess if the effects shown in these studies [13,17,24,25,28,36,43,45] are real. Another important issue in studies investigating colposcopy and colposcopically-guided cervical biopsies is the experience of the colposcopists included in these studies. Only a minority of the studies included in this review have addressed this issue [31,33,38]. In the absence of information regarding the experience of the colposcopists, it cannot be ruled out that some of the studies included in this review have a limited external validity and results may not be applicable to settings with a high proportion of novices or exclusively expert settings.
In one of the studies included in our review [15], it was found that random biopsies are effective for identifying CIN2+ lesions, although a policy of non-targeted biopsies for women referred for colposcopy at the lowest level of risk and a completely normal colposcopic impression are not generally recommended. We do not recommend implementing a general policy of random biopsies. However, the data in Jespersen’s study [15] suggest that under specific circumstances such as in women with cytology of LSIL or ASCUS and a normal colposcopic impression, random biopsies my result in a higher yield of CIN2+. On the other hand, no study included in our systematic review indicates that random biopsies are of any value when a minor or major change lesion is visible. Another issue is that the level of colposcopic expertise has not been incorporated in the Jespersen study. Thus, the usefulness of random biopsies may be limited to unexperienced colposcopists who find it harder to correctly identify acetowhite and/or iodine-negative cervical lesions. Although not proven in a clinical trial, it seems reasonable to advise young colposcopists to use biopsies more liberally than experienced colleagues do.
An up-to-date recommendation for diagnostic interventions in women with suspected cervical dysplasia is as follows: Based on seven RCTs [18,20,21,22,23,24,25] we recommend intravenous or intracervical lidocaine for pain reduction during colposcopically-directed cervical biopsies. We do not recommend topical lidocaine [18,23], music, or video colposcopy (with the patient watching the procedure) during colposcopy [20,22]. Monsel’s solution might be used to control bleeding after cervical biopsies [19]. The acetic acid test should be scored 1 min after the application of acetic acid [14] and should be followed by Lugol’s iodine test for an optimal yield of LSIL/HSIL [16]. In women with cytology of LSIL or ASCUS and a normal colposcopic impression, 4 random cervical biopsies are useful [15].
An up-to-date recommendation for therapeutic interventions in women with cervical dysplasia is as follows: LEEP/LLETZ remains the standard and techniques such as SWETZ, C-LETZ, and TCBEE are not superior [26,27,28,31]. LEEP/LLETZ should be performed under local anesthesia and with direct colposcopic vision [33]. Spray coagulation for intra-operative bleeding control during LEEP/LLETZ is faster but equally effective compared to forced coagulation [29]. Cryotherapy and thermoablation might be used in women with LSIL, especially in women with HIV infection [30,32,36,39], but LEEP/LLETZ remains the standard for HSIL [34]. Topical imiquimod applied to the cervix or in the vagina seems to be safe and efficacious but remains an experimental procedure [40,45].
We also took care to see what the future holds for the management of women with cervical dysplasia. Among the studies currently enlisted at clinicaltrials.gov, the most exciting aspects are whether or not trichloracetic acid and pembrolizumab, a very cheap and a very expensive drug, respectively, will be added to the standard armamentarium of treating cervical dysplasia. In addition, reliable data from prospective studies will become available deciding whether it is safe to manage women with LSIL/HSIL with surveillance and for how long. Finally, data from RCTs will answer the question whether intra-operative Lugol’s iodine test during LEEP/LLETZ is useful for the definition of optimal resection margins and whether a limited form of LEEP only resecting biopsy-proven lesions instead of the whole transformation zone is safe. In summary, data will become available within the next 3–5 y further refining and optimizing the surgical and non-surgical treatment of cervical dysplasia.
5. Future Research Needs
Research on the diagnosis and therapy of cervical dysplasia is in constant progress. To underline this, we identified 27 ongoing clinical trials addressing various unresolved issues. For example, eight ongoing studies will assess different surgical techniques, among them intra-operative iodine test during LEEP/LLETZ, virtual reality-assisted LEEP/LLETZ, partial resection of the cervix compared to full LLETZ, and thermal ablation. Clearly, improving cervical surgery is a major medical research need and should be a focus of further clinical trials based on the high number of women who have to undergo cervical procedures. Second, conservative therapies obviating the need for surgery all together should be another important research focus. It will be important to see if substances such as trichloracetic acid, curcumin, estradiol, or pembrolizumab can effectively treat cervical dysplasia and spare affected women the risk of adverse pregnancy outcomes associated with cervical surgery. Finally, the potential therapeutic efficacy of HPV vaccines and their potential to reduce the recurrence risk after complete therapy of cervical dysplasia are another important field of future research.
6. Conclusions
In conclusion, we found that tremendous progress has been made in the last decade regarding both diagnostic interventions as well as therapeutic interventions for women with cervical dysplasia. Based on >30 controlled clinical trials, we were able to formulate specific and evidence-based recommendations.
Author Contributions
Conceptualization, C.B.T. and G.A.R.; methodology, C.B.T. and G.A.R.; formal analysis, J.M.H. and G.A.R.; investigation, J.M.H. and C.B.T.; data curation, J.M.H. and G.A.R.; writing—original draft preparation, J.M.H., G.A.R., and C.B.T.; writing—review and editing, G.A.R. and C.B.T.; visualization, G.A.R.; supervision, C.B.T. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data presented in this study are available from the corresponding author upon reasonable request.
Acknowledgments
We acknowledge support by the Open Access Publication Funds of the Ruhr-Universität Bochum.
Conflicts of Interest
The authors declare no conflict of interest.
Abbreviations
ASCUS, atypical squamous cells of undetermined significance; C-LETZ, contour-loop excision of the transformation zone; CI, confidence interval; CIN, cervical intraepithelial neoplasia; HPV, Human Papilloma Virus; HSIL, high-grade squamous intraepithelial lesions; LEEP, large loop excision of the transformation zone; LLETZ, large loop excision of the transformation zone; LSIL, low-grade squamous intraepithelial lesions; MD, mean difference; OR, odds ratio; PCT, non-randomized controlled trial; PICO, Population/Problem-Intervention/Exposure-Comparison-Outcome; PRISMA, Preferred Reporting Items for Systematic Reviews and Meta-Analyses; RCT, randomized controlled trial; RR, relative risk; SWETZ, Straight Wire Excision of the Transformation Zone; TCBEE, True Cone Biopsy Electrode Excision; and US, United States.
References
- Curry, S.J.; Krist, A.H.; Owens, D.K.; Barry, M.J.; Caughey, A.B.; Davidson, K.W.; Doubeni, C.A.; Epling, J.W.; Kemper, A.R.; Kubik, M.; et al. Screening for Cervical Cancer: US Preventive Services Task Force Recommendation Statement. JAMA 2018, 320, 674–686. [Google Scholar] [CrossRef] [Scilit]
- Loopik, D.L.; Bentley, H.A.; Eijgenraam, M.N.; IntHout, J.; Bekkers, R.L.M.; Bentley, J.R. The Natural History of Cervical Intraepithelial Neoplasia Grades 1, 2, and 3: A Systematic Review and Meta-analysis. J. Low. Genit. Tract Dis. 2021, 25, 221–231. [Google Scholar] [CrossRef] [Scilit]
- Jain, M.A.; Limaiem, F. Cervical Intraepithelial Squamous Cell Lesion; StatPearls: Treasure Island, FL, USA, 2021.
- American Cancer Society. Cancer Facts & Figures 2021. Available online: https://www.cancer.org/content/dam/cancer-org/research/cancer-facts-and-statistics/annual-cancer-facts-and-figures/2021/cancer-facts-and-figures-2021.pdf (accessed on 4 April 2022).
- Liverani, C.A.; Di Giuseppe, J.; Clemente, N.; Delli Carpini, G.; Monti, E.; Fanetti, F.; Bolis, G.; Ciavattini, A. Length but not transverse diameter of the excision specimen for high-grade cervical intraepithelial neoplasia (CIN 2-3) is a predictor of pregnancy outcome. Eur. J. Cancer Prev. 2016, 25, 416–422. [Google Scholar] [CrossRef] [Scilit]
- Bitonti, G.; Clemente, N.; Del Fabro, A.; Manna, P.; Buttignol, M.; Cadel, M.; Di Carlo, C.; Giorda, G.; Zullo, F.; Sopracordevole, F. CIN 2 in childbearing-age women: May colposcopy help in choosing the proper management? Minerva Obstet. Gynecol. 2021. [Google Scholar] [CrossRef] [Scilit]
- Monti, M.; D’Aniello, D.; Scopelliti, A.; Tibaldi, V.; Santangelo, G.; Colagiovanni, V.; Giannini, A.; Di Donato, V.; Palaia, I.; Perniola, G.; et al. Relationship between cervical excisional treatment for cervical intraepithelial neoplasia and obstetrical outcome. Minerva Obstet. Gynecol. 2021, 73, 233–246. [Google Scholar] [CrossRef] [Scilit]
- Kyrgiou, M.; Athanasiou, A.; Paraskevaidi, M.; Mitra, A.; Kalliala, I.; Martin-Hirsch, P.; Arbyn, M.; Bennett, P.; Paraskevaidis, E. Adverse obstetric outcomes after local treatment for cervical preinvasive and early invasive disease according to cone depth: Systematic review and meta-analysis. BMJ 2016, 354, i3633. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Thomas, J.; Kneale, D.; McKenzie, J.E.; Brennan, S.E.; Bhaumik, S. Chapter 2: Determining the scope of the review and the questions it will address. In Cochrane Handbook for Systematic Reviews of Interventions: Version 6.3 (Updated February 2022), 2nd ed.; Higgins, J., Thomas, J., Chandler, J., Cumpston, M., Li, T., Page, M., Welch, V., Eds.; John Wiley & Sons: Chichester, UK, 2022. [Google Scholar]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.-Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit]
- Slim, K.; Nini, E.; Forestier, D.; Kwiatkowski, F.; Panis, Y.; Chipponi, J. Methodological index for non-randomized studies (MINORS): Development and validation of a new instrument. ANZ J. Surg. 2003, 73, 712–716. [Google Scholar] [CrossRef] [Scilit]
- Bogani, G.; Serati, M.; Cromi, A.; Di Naro, E.; Casarin, J.; Pinelli, C.; Rossi, T.; Ghezzi, F. Local anesthetic versus forced coughing at colposcopic-guided biopsy: A prospective study. Eur. J. Obstet. Gynecol. Reprod. Biol. 2014, 181, 15–19. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Tempfer, C.B.; Burgard, L.; Rehman, S.; Rezniczek, G.A. How long is too long? Application of acetic acid during colposcopy: A prospective study. Am. J. Obstet. Gynecol. 2020, 223, 101.e1–101.e8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jespersen, M.M.; Booth, B.B.; Petersen, L.K. Can biopsies be omitted after normal colposcopy in women referred with low-grade cervical cytology? A prospective cohort study. BMC Women’s Health 2021, 21, 394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rezniczek, G.A.; Ertan, S.; Rehman, S.; Tempfer, C.B. Sequential Application of Lugol’s Iodine Test after Acetic Acid for Detecting Cervical Dysplasia: A Prospective Cohort Study. Diagnostics 2021, 11, 1598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Niu, J.; Cheng, M.; Hong, Z.; Ling, J.; Di, W.; Gu, L.; Qiu, L. The effect of 5-Aminolaevulinic Acid Photodynamic Therapy versus CO2 laser in the Treatment of Cervical Low-grade Squamous Intraepithelial Lesions with High-Risk HPV Infection: A non-randomized, controlled pilot study. Photodiagnosis Photodyn. Ther. 2021, 36, 102548. [Google Scholar] [CrossRef] [Scilit]
- Öz, M.; Korkmaz, E.; Cetinkaya, N.; Baş, S.; Özdal, B.; Meydanl, M.M.; Güngör, T. Comparison of Topical Lidocaine Spray with Placebo for Pain Relief in Colposcopic Procedures: A Randomized, Placebo-Controlled, Double-Blind Study. J. Low. Genit. Tract Dis. 2015, 19, 212–214. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Rezniczek, G.A.; Tettenborn, Z.; Hefler, L.A.; Tempfer, C.B. Efficacy of Monsel Solution After Cervical Biopsy: A Randomized Trial. J. Low. Genit. Tract Dis. 2016, 20, 312–316. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Alici, F.; Tempfer, C.B.; Seebacher, V.; Rezniczek, G.A. Video Colposcopy for Reducing Patient Anxiety During Colposcopy: A Randomized Controlled Trial. Obstet. Gynecol. 2017, 130, 411–419. [Google Scholar] [CrossRef] [Scilit]
- Kiviharju, M.; Kalliala, I.; Nieminen, P.; Dyba, T.; Riska, A.; Jakobsson, M. Pain Sensation During Colposcopy and Cervical Biopsy, with or without Local Anesthesia: A Randomized Trial. J. Low. Genit. Tract Dis. 2017, 21, 102–107. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Alici, F.; Tempfer, C.B.; Rath, K.; Nar, K.; Rezniczek, G.A. Mozart for Reducing Patient Anxiety During Colposcopy: A Randomized Controlled Trial. Obstet. Gynecol. 2018, 132, 1047–1055. [Google Scholar] [CrossRef] [Scilit]
- Karaman, E.; Kolusarı, A.; Alkış, İ.; Çetin, O. Comparison of topical lidocaine spray with forced coughing in pain relief during colposcopic biopsy procedure: A randomised trial. J. Obstet. Gynaecol. 2019, 39, 534–538. [Google Scholar] [CrossRef] [Scilit]
- Comba, C.; Demirayak, G.; Erdogan, S.V.; Karaca, I.; Demir, O.; Guler, O.; Ozdemir, I.A. Comparison of pain and proper sample status according to usage of tenaculum and analgesia: A randomized clinical trial. Obstet. Gynecol. Sci. 2020, 63, 506–513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Topdaği, Y.E.; Topdagi Yilmaz, E.P.; Aydin, M.E.; Ates, I.; Oral Ahiskalioglu, E. Does intravenous lidocaine added to nonsteroidal anti-inflammatory drugs reduce pain during colposcopy? A prospective randomized double-blind study. Ginekol. Pol. 2021, 92, 844–849. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boonlikit, S.; Thitisagulwong, S. C-LETZ versus large loop excision of the transformation zone for the treatment of cervical intraepithelial neoplasia: A randomized controlled trial. Arch. Gynecol. Obstet. 2012, 286, 1173–1179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Camargo, M.J.; Russomano, F.B.; Tristão, M.A.; Huf, G.; Prendiville, W. Large loop versus straight-wire excision of the transformation zone for treatment of cervical intraepithelial neoplasia: A randomised controlled trial of electrosurgical techniques. BJOG 2015, 122, 552–557. [Google Scholar] [CrossRef] [Scilit]
- Russomano, F.; Tristao, M.A.P.; Côrtes, R.; de Camargo, M.J. A comparison between type 3 excision of the transformation zone by straight wire excision of the transformation zone (SWETZ) and large loop excision of the transformation zone (LLETZ): A randomized study. BMC Womens. Health 2015, 15, 12. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Mavrommati, G.; Foerster, C.; Rezniczek, G.A.; Hefler, L.A.; Tempfer, C.B. Spray Versus Forced Coagulation in Large Loop Excision of the Transformation Zone: A Randomized Trial. J. Low. Genit. Tract Dis. 2016, 20, 169–173. [Google Scholar] [CrossRef] [Scilit]
- Firnhaber, C.; Swarts, A.; Goeieman, B.; Rakhombe, N.; Mulongo, M.; Williamson, A.-L.; Michelow, P.; Ramotshela, S.; Faesen, M.; Levin, S.; et al. Cryotherapy Reduces Progression of Cervical Intraepithelial Neoplasia Grade 1 in South African HIV-Infected Women: A Randomized, Controlled Trial. J. Acquir. Immune Defic. Syndr. 2017, 76, 532–538. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Rezniczek, G.A.; El-Fizazi, N.; Tempfer, C.B. Large Loop Excision of the Transformation Zone Versus True Cone Biopsy Electrode Excision: A Randomized Trial. J. Low. Genit. Tract Dis. 2017, 21, 272–278. [Google Scholar] [CrossRef] [Scilit]
- Smith, J.S.; Sanusi, B.; Swarts, A.; Faesen, M.; Levin, S.; Goeieman, B.; Ramotshela, S.; Rakhombe, N.; Williamson, A.L.; Michelow, P.; et al. A randomized clinical trial comparing cervical dysplasia treatment with cryotherapy vs. loop electrosurgical excision procedure in HIV-seropositive women from Johannesburg, South Africa. Am. J. Obstet. Gynecol. 2017, 217, 183.e1–183.e11. [Google Scholar] [CrossRef] [Scilit]
- Hilal, Z.; Rezniczek, G.A.; Alici, F.; Kumpernatz, A.; Dogan, A.; Alieva, L.; Tempfer, C.B. Loop electrosurgical excision procedure with or without intraoperative colposcopy: A randomized trial. Am. J. Obstet. Gynecol. 2018, 219, 377.e1–377.e7. [Google Scholar] [CrossRef] [Scilit]
- Greene, S.A.; de Vuyst, H.; John-Stewart, G.C.; Richardson, B.A.; McGrath, C.J.; Marson, K.G.; Trinh, T.T.; Yatich, N.; Kiptinness, C.; Cagle, A.; et al. Effect of Cryotherapy vs. Loop Electrosurgical Excision Procedure on Cervical Disease Recurrence Among Women with HIV and High-Grade Cervical Lesions in Kenya: A Randomized Clinical Trial. JAMA 2019, 322, 1570–1579. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kolben, T.M.; Etzel, L.T.; Bergauer, F.; Hagemann, I.; Hillemanns, P.; Repper, M.; Kaufmann, A.M.; Sotlar, K.; Kolben, T.; Helms, H.J.; et al. A randomized trial comparing limited-excision conisation to Large Loop Excision of the Transformation Zone (LLETZ) in cervical dysplasia patients. J. Gynecol. Oncol. 2019, 30, e42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Banerjee, D.; Mandal, R.; Mandal, A.; Ghosh, I.; Mittal, S.; Muwonge, R.; Lucas, E.; Basu, P. A Prospective Randomized Trial to Compare Safety, Acceptability and Efficacy of Thermal Ablation and Cryotherapy in a Screen and Treat Setting. Asian Pac. J. Cancer Prev. 2020, 21, 1391–1398. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chong, G.O.; Lee, Y.H.; Jeon, S.Y.; Yang, H.-Y.; An, S.-H. Efficacy of a chitosan tampon in the loop electrosurgical excision procedure: A prospective randomized controlled study. Sci. Rep. 2020, 10, 6017. [Google Scholar] [CrossRef] [Scilit]
- Rezniczek, G.A.; Hecken, J.M.; Rehman, S.; Dogan, A.; Tempfer, C.B.; Hilal, Z. Syringe or mask? Loop electrosurgical excision procedure under local or general anesthesia: A randomized trial. Am. J. Obstet. Gynecol. 2020, 223, 888.e1–888.e9. [Google Scholar] [CrossRef] [Scilit]
- Duan, L.; Du, H.; Belinson, J.L.; Liu, Z.; Xiao, A.; Liu, S.; Zhao, L.; Wang, C.; Qu, X.; Wu, R. Thermocoagulation versus cryotherapy for the treatment of cervical precancers. J. Obstet. Gynaecol. Res. 2021, 47, 279–286. [Google Scholar] [CrossRef] [Scilit]
- Fonseca, B.O.; Possati-Resende, J.C.; Salcedo, M.P.; Schmeler, K.M.; Accorsi, G.S.; Fregnani, J.H.T.G.; Antoniazzi, M.; Pantano, N.P.; Santana, I.V.V.; Matsushita, G.M.; et al. Topical Imiquimod for the Treatment of High-Grade Squamous Intraepithelial Lesions of the Cervix: A Randomized Controlled Trial. Obstet. Gynecol. 2021, 137, 1043–1053. [Google Scholar] [CrossRef] [Scilit]
- Firnhaber, C.; Swarts, A.; Jezile, V.; Mulongo, M.; Goeieman, B.; Williams, S.; Faesen, M.; Michelow, P.; Wilkin, T. Human Papillomavirus Vaccination Prior to Loop Electroexcision Procedure Does Not Prevent Recurrent Cervical High-grade Squamous Intraepithelial Lesions in Women Living with Human Immunodeficiency Virus: A Randomized, Double-blind, Placebo-controlled Trial. Clin. Infect. Dis. 2021, 73, e2211–e2216. [Google Scholar] [CrossRef] [Scilit]
- Gungorduk, K.; Ozdemir, A.; Sahin, O. Optimal timing of the loop electrosurgical excision procedure according to different phases of the menstrual cycle. J. Gynecol. Obstet. Hum. Reprod. 2021, 50, 101888. [Google Scholar] [CrossRef] [Scilit]
- Vieira, M.D.A.; de Araújo, R.L.C.; Da Cunha Andrade, C.E.M.; Schmidt, R.L.; Filho, A.L.; Reis, R.D. A randomized clinical trial of a new anti-cervical stenosis device after conization by loop electrosurgical excision. PLoS ONE 2021, 16, e0242067. [Google Scholar] [CrossRef] [Scilit]
- Rezniczek, G.A.; Neghabian, N.; Rehman, S.; Tempfer, C.B. Video colposcopy versus headlight for large loop excision of the transformation zone (LLETZ): A randomised trial. Arch. Gynecol. Obstet. 2022, 305, 415–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Polterauer, S.; Reich, O.; Widschwendter, A.; Hadjari, L.; Bogner, G.; Reinthaller, A.; Joura, E.; Trutnovsky, G.; Ciresa-Koenig, A.; Ganhoer-Schimboeck, J.; et al. Topical imiquimod compared with conization to treat cervical high-grade squamous intraepithelial lesions: Multicenter, randomized controlled trial. Gynecol. Oncol. 2022, 165, 23–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martin-Hirsch, P.P.L.; Bryant, A. Interventions for preventing blood loss during the treatment of cervical intraepithelial neoplasia. Cochrane Database Syst. Rev. 2013, CD001421. [Google Scholar] [CrossRef] [Scilit]
- Gajjar, K.; Martin-Hirsch, P.P.L.; Bryant, A.; Owens, G.L. Pain relief for women with cervical intraepithelial neoplasia undergoing colposcopy treatment. Cochrane Database Syst. Rev. 2016, 7, CD006120. [Google Scholar] [CrossRef] [Scilit]
- Santesso, N.; Mustafa, R.A.; Wiercioch, W.; Kehar, R.; Gandhi, S.; Chen, Y.; Cheung, A.; Hopkins, J.; Khatib, R.; Ma, B.; et al. Systematic reviews and meta-analyses of benefits and harms of cryotherapy, LEEP, and cold knife conization to treat cervical intraepithelial neoplasia. Int. J. Gynaecol. Obstet. 2016, 132, 266–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, W.; Zhang, A.; Sun, W.; Yue, Y.; Li, H. Efficacy and safety of photodynamic therapy for cervical intraepithelial neoplasia and human papilloma virus infection: A systematic review and meta-analysis of randomized clinical trials. Medicine 2018, 97, e10864. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Alessandro, P.; Arduino, B.; Borgo, M.; Saccone, G.; Venturella, R.; Di Cello, A.; Zullo, F. Loop Electrosurgical Excision Procedure versus Cryotherapy in the Treatment of Cervical Intraepithelial Neoplasia: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Gynecol. Minim. Invasive Ther. 2018, 7, 145–151. [Google Scholar] [CrossRef] [Scilit]
- Unanyan, A.; Pivazyan, L.; Davydova, J.; Murvatova, K.; Khrapkova, A.; Movsisyan, R.; Ishchenko, A.; Ishchenko, A. Efficacy of photodynamic therapy in women with HSIL, LSIL and early stage squamous cervical cancer: A systematic review and meta-analysis. Photodiagnosis Photodyn. Ther. 2021, 36, 102530. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).