


Abstract
This manuscript proposes an integrated system for treating hospital solid waste (H.S.W.) consisting of an incineration and frictional sterilization system capable of operating during normal and emergency situations. We analyzed the benefits of integrating different hospital solid waste (H.S.W.) treatment systems with the existing stand-alone incineration system, with a particular emphasis on the thermal friction sterilization integration system. The objective was to define the economic advantages and benefits in terms of resources recovery of using the thermal frictional sterilization–incineration integrated system during the hospital’s normal and emergency/pandemic operating conditions. We modeled three modeling scenarios based on normal and emergency operating conditions. The results show that the H.S.W. was composed of 74% general H.S.W. Existing incineration systems would be the most expensive process because the sanitary transportation cost represented approximately 96% of the H.S.W. costs. The hospital would realize 40–61% savings relative to the existing method if the integrated incineration–frictional systems were implemented to treat 50–70% of H.S.W.; the savings were better than in other scenarios. Proposed scenario 3 had a much better resources recovery factor than scenarios 1 and 2. This modeling study showed that a thermal frictional sterilization–incineration system could work well even under emergency conditions if the H.S.W. in-house sorting/transportation/storage process is modified to cater to other H.S.W. treatment/sterilization systems.
1. Introduction
The hospital solid waste (H.S.W.) and treatment process is a topic of concern to interested parties and society, especially when COVID-19 is prevalent and the pandemic persists. The current pandemic has widened the potential sources of H.S.W. to include hospitals, residential houses (because of current isolation practices), and public facilities used for medical prophylactic or treatment purposes. In other cases, H.S.W. has been found in the streets [1]. It is evident that the COVID-19 pandemic period has strained the existing—and thus, any future—disposal and transportation system [2]. Statistics associated with hospital waste and its relative forecasts have been presented [3,4,5,6]. Therefore, the majority of stakeholders (including citizens) would appreciate the design and implementation of a resilient and effective H.S.W. treatment process. Additionally, the product benefits and environment objectives need to be considered together [7].
Effective hospital waste management practices have been implemented to date [8]. Ranjbari et al. [9] observed that hospital solid waste minimization and their respective management systems have been priority research topics. However, most medical waste management systems have been strained during the pandemic because of unpredictability and the excessive mass waste generation [10,11]. The large-scale treatment of hospital waste could be an effective H.S.W. disposal process, and the operation could be strained when an unpredictable situation or pandemic strikes [12,13]. In addition to unpredictability, hospital solid waste has a certain level of risk for hospital workers, patients and the community at large [14,15,16].
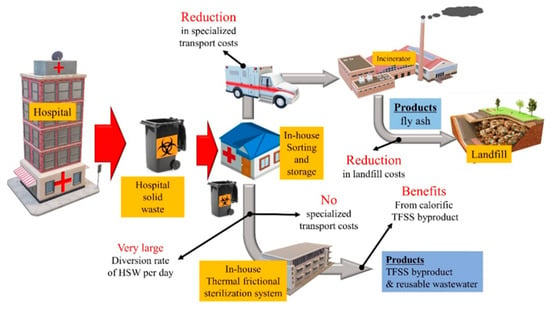
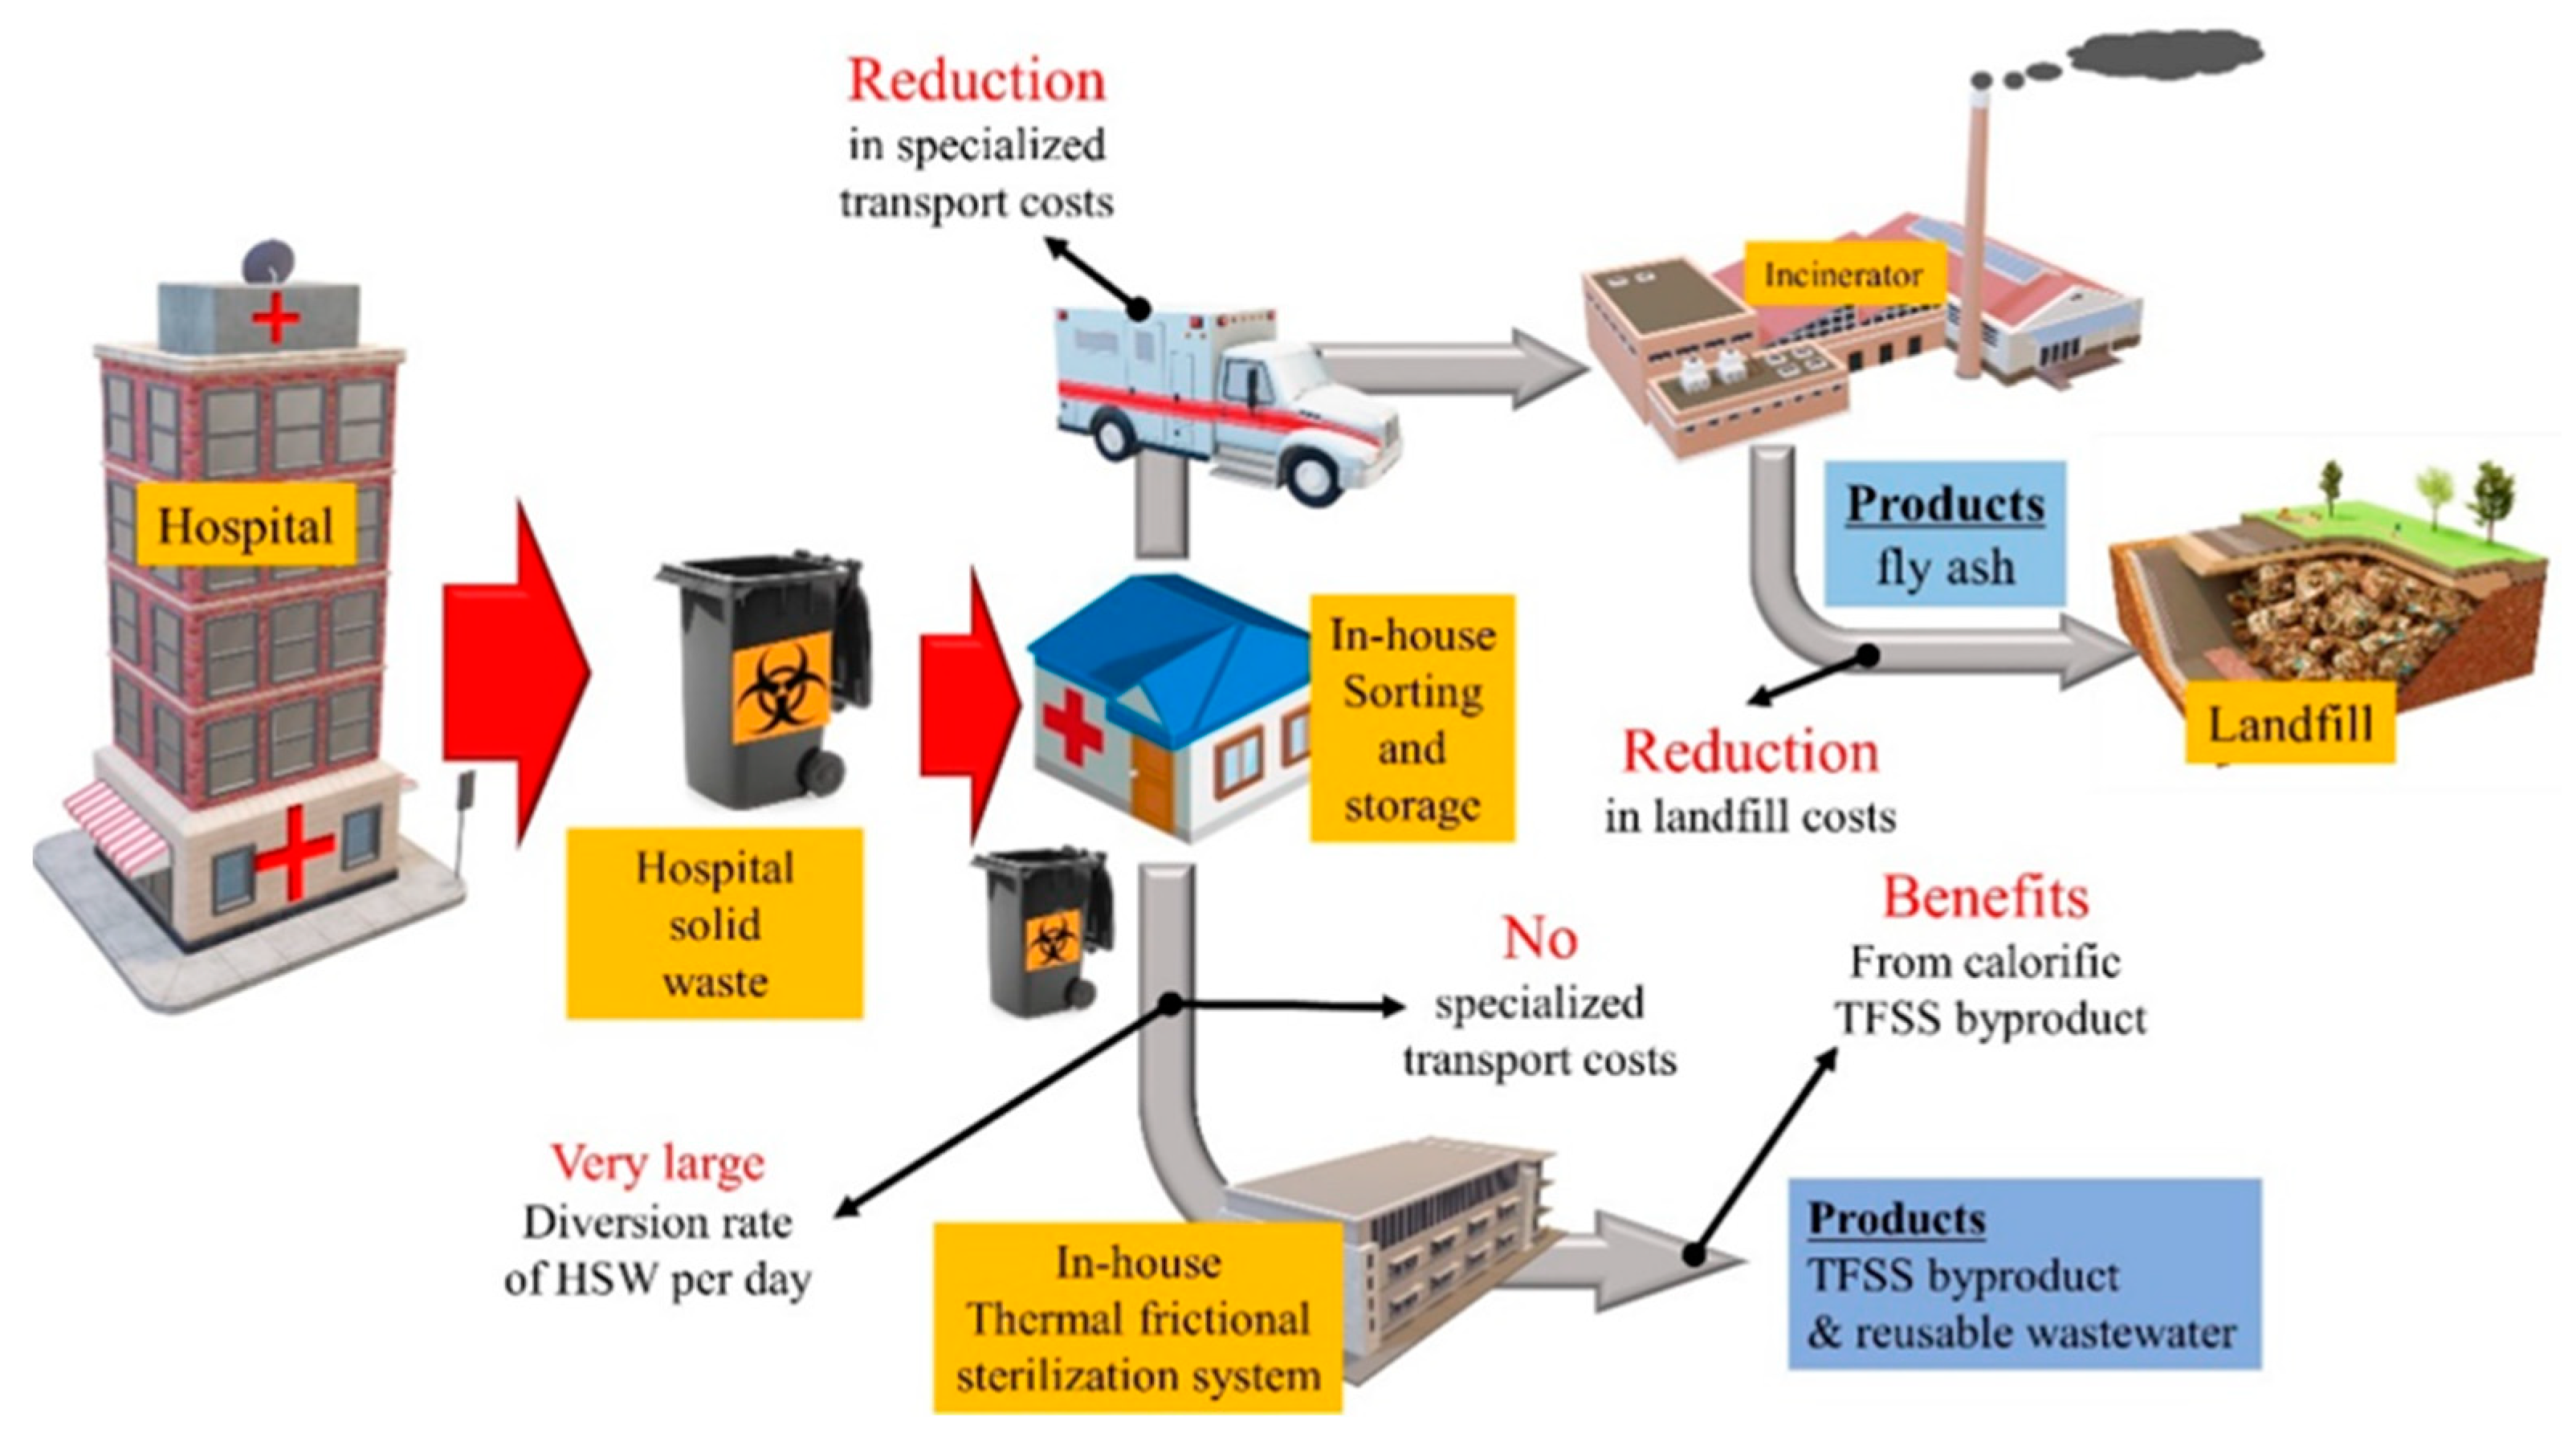
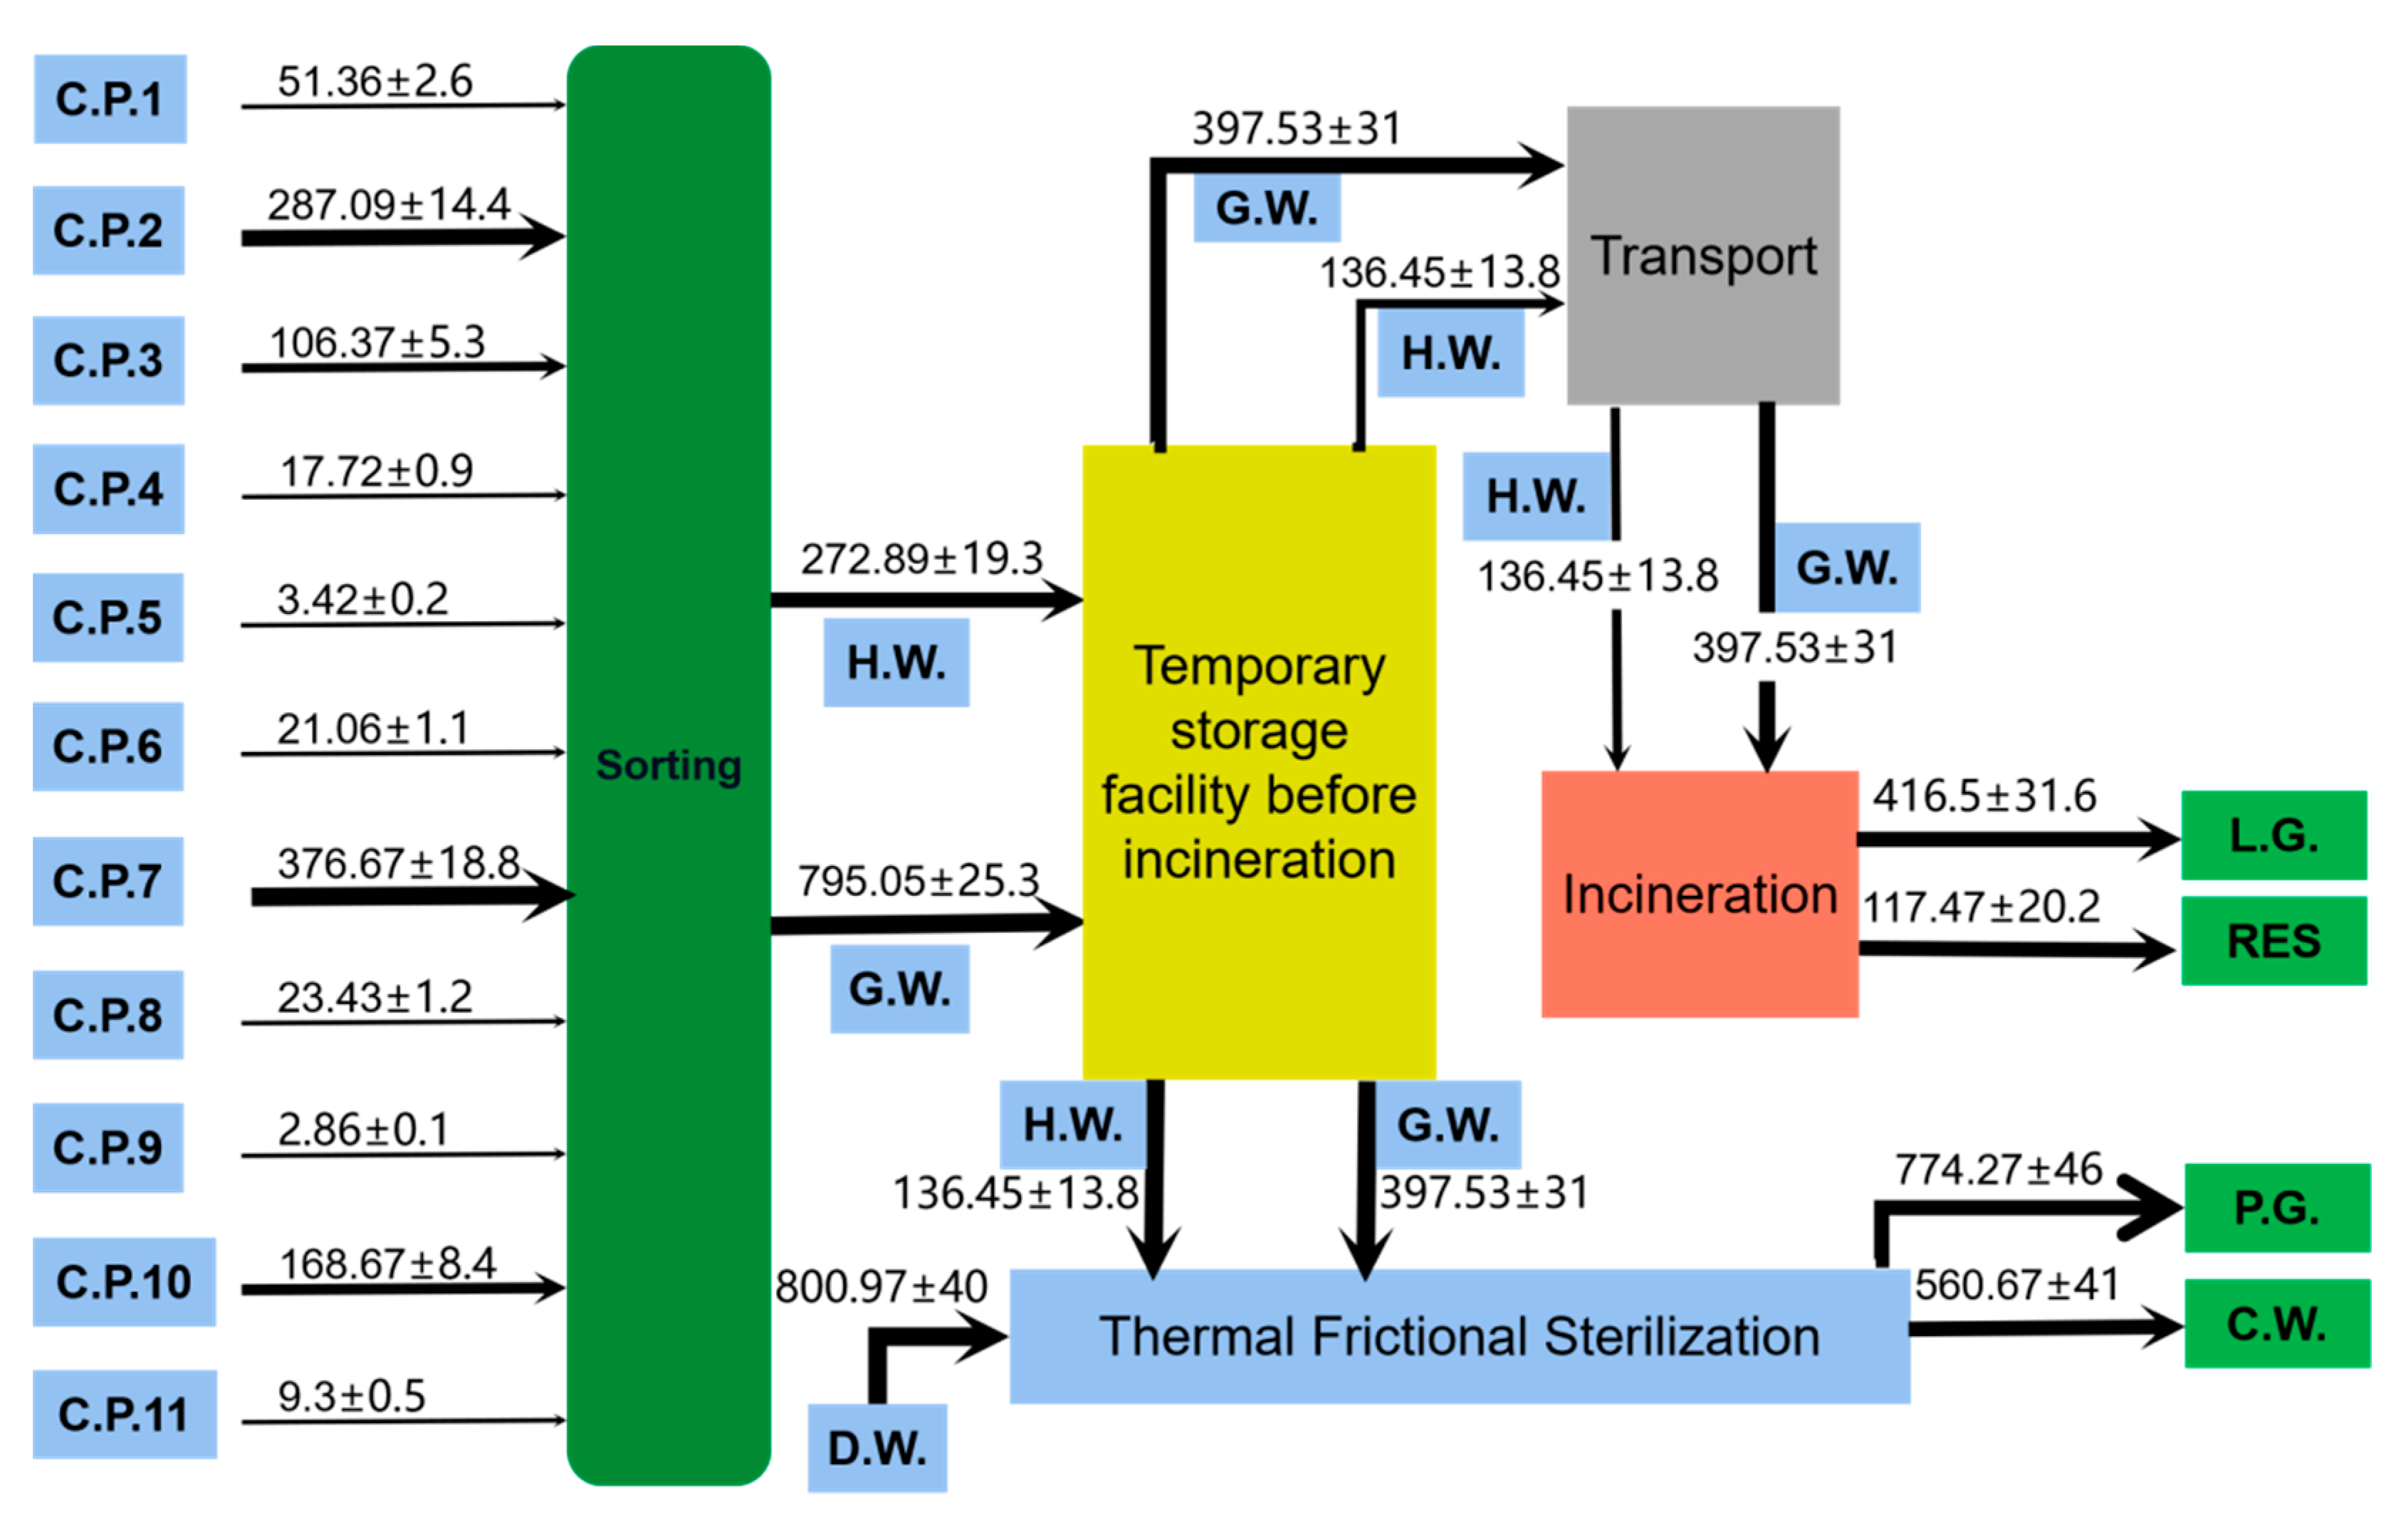
In light of the problems mentioned above, the integration of the existing H.S.W. treatment system (i.e., incineration system) with other custom-made proven technologies could be the way forward. H.S.W. treatment integration will require that H.S.W. should be sorted (i.e., via an improved or modified sorting system) at source, thus reducing the infectious/hazardous waste component. Usually, it is the infectious and hazardous (including chemical) H.S.W. that will require incineration or a specialized treatment process. Therefore, an effective sorting process will generate waste that could be treated using other custom-made treatment processes. Such custom-made treatment processes could include the thermal frictional sterilization (TFS) process developed by Newster Srl [17]. Newster sterilization systems (N.W. series) are low-environment impact sterilizing units capable of serving hospitals with a capacity of 150~600 beds, and achieving 75% H.S.W. volume reduction, 25% initial weight reduction, and 28-day sterilization effectiveness. Further information related to the technology can be found in [18,19]. Although Newster sterilization systems (N.W. series) may require 10~40 kWh to treat 10~60 kg of H.S.W. and the compactness of the treatment systems, the produced products have some calorific value. Therefore, hospitals could gain in terms of economic value by using the waste for energy; the preliminary analysis of the samples obtained from one of the healthcare centers using the equipment showed that the waste has an average calorific value of 4100 kcal/kg. Furthermore, part of the hospital solid waste has a calorific value, meaning that energy recovery is possible [20,21]. The conceptual integration process we propose (Figure 1) supposes that several H.S.W. streams from several departments could be sorted and diverted for sterilization. Thus, sorting and in-house transportation/storage is streamlined to separate the sterilizable H.S.W. and is followed by impromptu TFS sterilization.
Figure 1.
Conceptual framework for incineration–TFS integration system.
Therefore, the lead time for treating the H.S.W. is reduced, and a large proportion of the H.S.W. is sterilized on time. By introducing the incineration–TFS integrated system, the overall storage space and facilities required for the H.S.W. could be reduced. Newster technology can also handle infectious waste, including bandages, polymer-based personal protective attires, liquids, and pathological waste, among others [18]. This means that the technology could treat both generous and hazardous H.S.W. Furthermore, a very high diversion rate of calorific H.S.W. will be inherent. Thus incineration, landfill, and specialized transportation costs will be reduced. Additionally, modular-type TFS systems have been designed to operate with varying H.S.W. capacity to be easily applied during emergencies.
All that said, introducing and integrating any new technology into the existing technology stream will require cost justification other than technological benefits. A cost–benefit analysis (C.B.A.) is a model of rationality capable of defining the beneficiaries and losses accrued if the aforementioned changes are implemented [22]. To date, Adhikari and Supakankunit [23] used C.B.A. to show that sorting at source together with alternative H.S.W. management system will reduce the overall monthly costs by 33%, and when the break-even point of C.B.A. reaches 40% of the H.S.W., the alternative H.S.W. treatment system will be used. Files at al. [24] studied the least-cost option for treating biomedical waste. Rashidian et al. [25] analyzed several pieces of equipment (including the Newster NW 10 equipment) to establish a cost-effective H.S.W. treatment method. The cost-effectiveness was computed for each piece of equipment, not as a combined treatment process. A similar cost-effectiveness analysis was conducted by Khashij et al. [26]. However, the unpredictability and excessive mass waste generation described previously [10,11] could strain any existing system. We have not yet come across any cost–benefit analysis when there’s excess H.S.W. to be treated and when integrated treatment systems are involved. As mentioned previously, the integrated system will include an existing incineration system and other proven H.S.W. treatment systems listed in [18]. This research aimed to determine the benefits accrued when different treatment options could be implemented under normal and during unpredictable emergency situations. The results and conclusions presented in this study contribute to the overall knowledge of H.S.W. treatment systems and their cost-effectiveness. In this manuscript, we describe the nature of the data we use in the modeling process, modeling scenarios, and their respective boundary conditions. We also describe the material flow analysis and how we compute the cost–benefit analysis and the resources conversion factor. Finally, the results from the modeling process will be presented in the results and discussion section.
2. Materials and Methods
2.1. Data Definition
This case study was based on a first-class comprehensive tertiary hospital A located in China. The hospital’s operational and statistical data used in this study are described in Table 1. This hospital uses a thermal incineration system for the disposal of the hospital solid waste. Furthermore, the H.S.W. is collected stored in a temporary storage facility in the hospital and treated at an off-site incineration facility. The incinerated ash generated from the incineration process is disposed of in landfills.
Table 1.
Hospital A monthly statistical data.
2.2. Boundaries and Scenarios
Several collection points, consisting of a group of departments, were considered in the modeling process, as shown in Table 2.
Table 2.
Collection points and classification of departments in Hospital A.
Each collection point was considered a functional collection point and source for modeling purposes. All the scenarios modeled in this study will be based on the normal operation of the hospital and emergency cases faced during the pandemic period. The following scenarios were considered for modeling purposes:
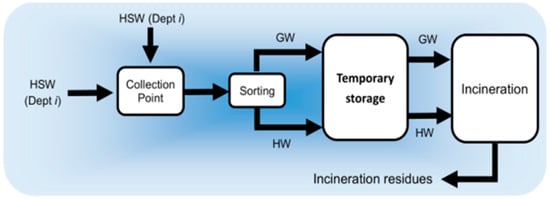
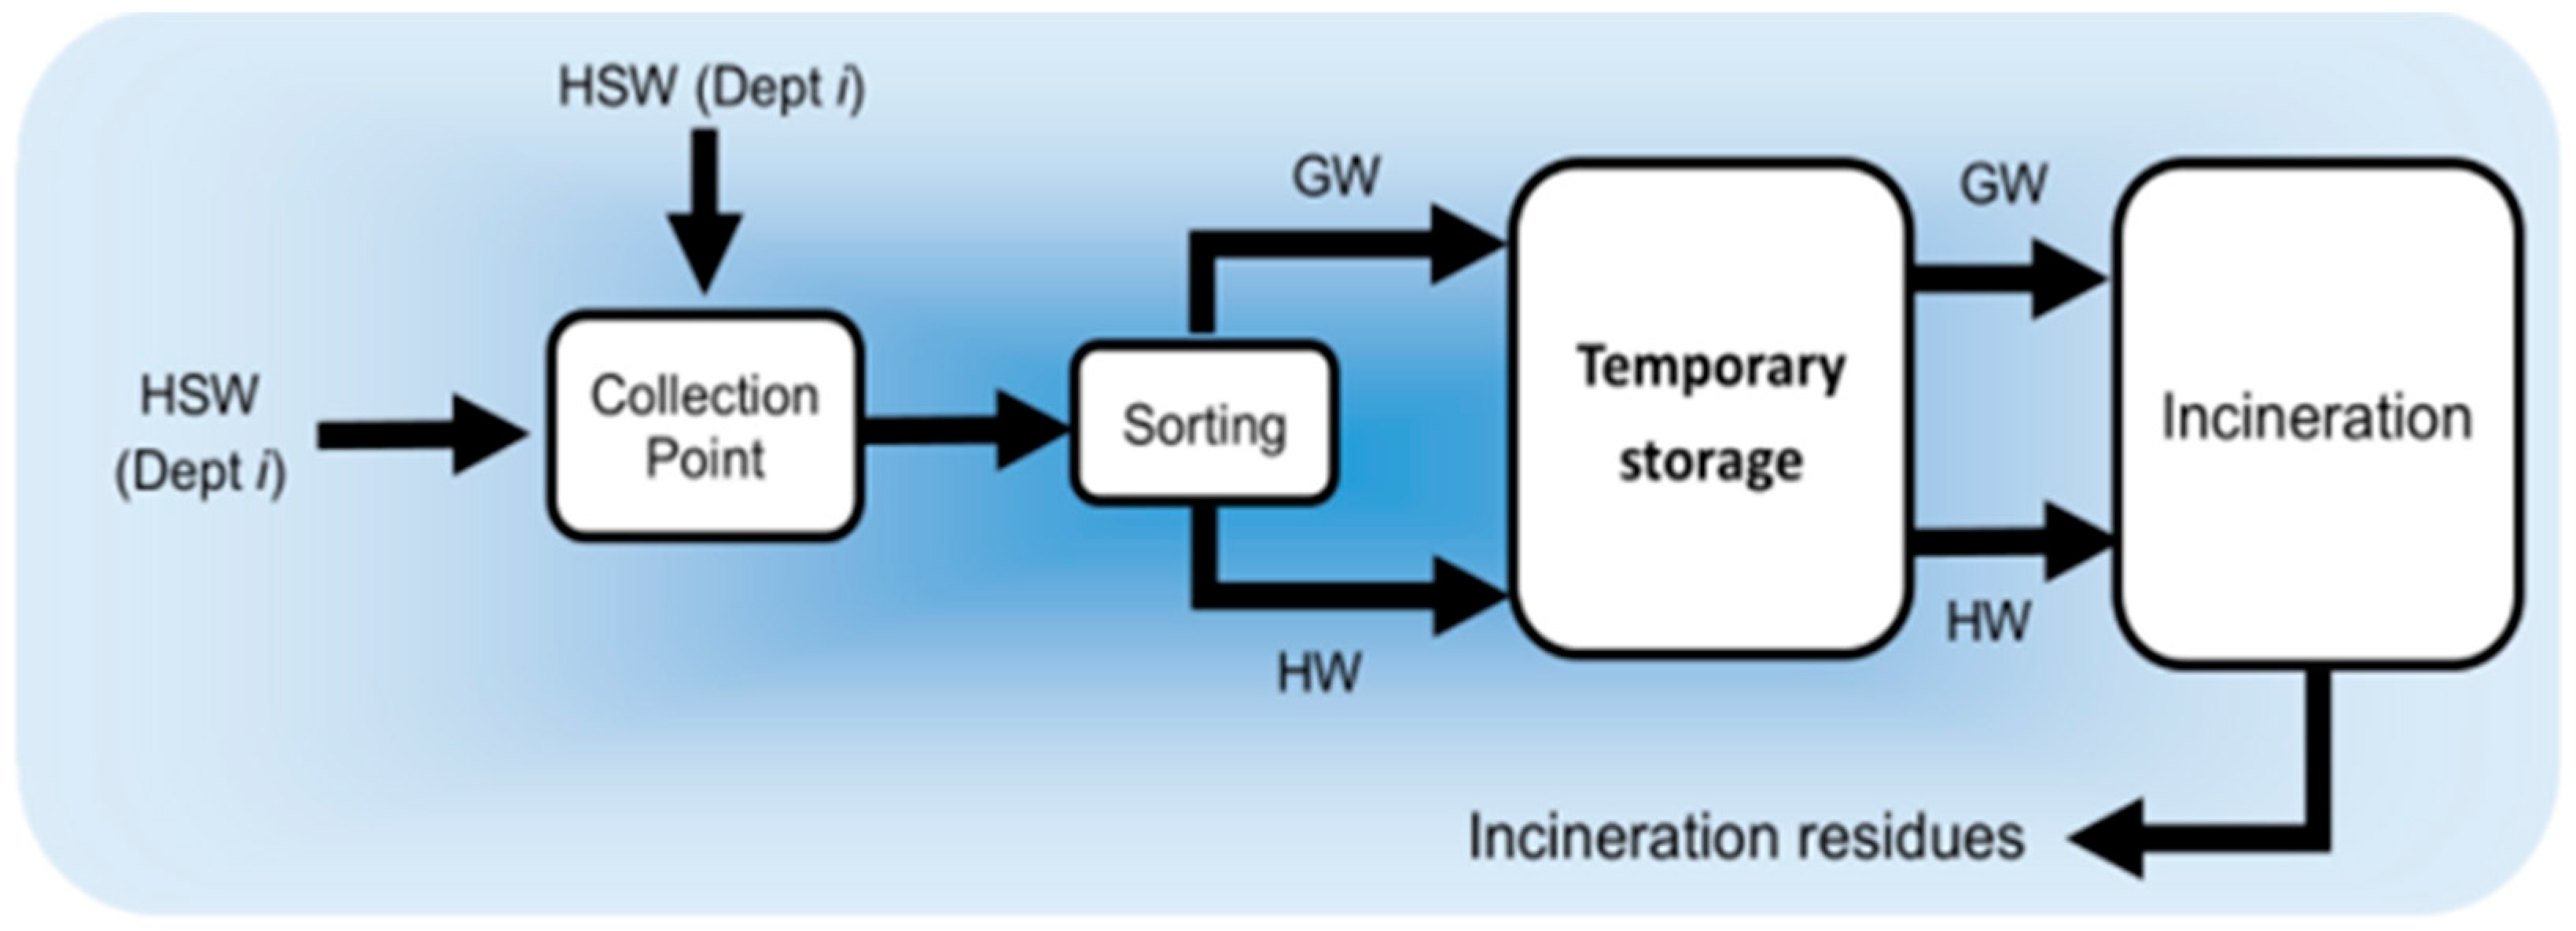
Scenario 1: All the generated H.S.W. is collected, sorted at the point of generation, and stored in a temporary storage facility in the hospital. The H.S.W. will be transported to an off-site specialized incineration facility daily after over 12 h of storage in the temporary storage facility (Figure 2). The modeling scenario applies to regular and emergency situations.
Figure 2.
H.S.W. disposal modeling scenario 1.
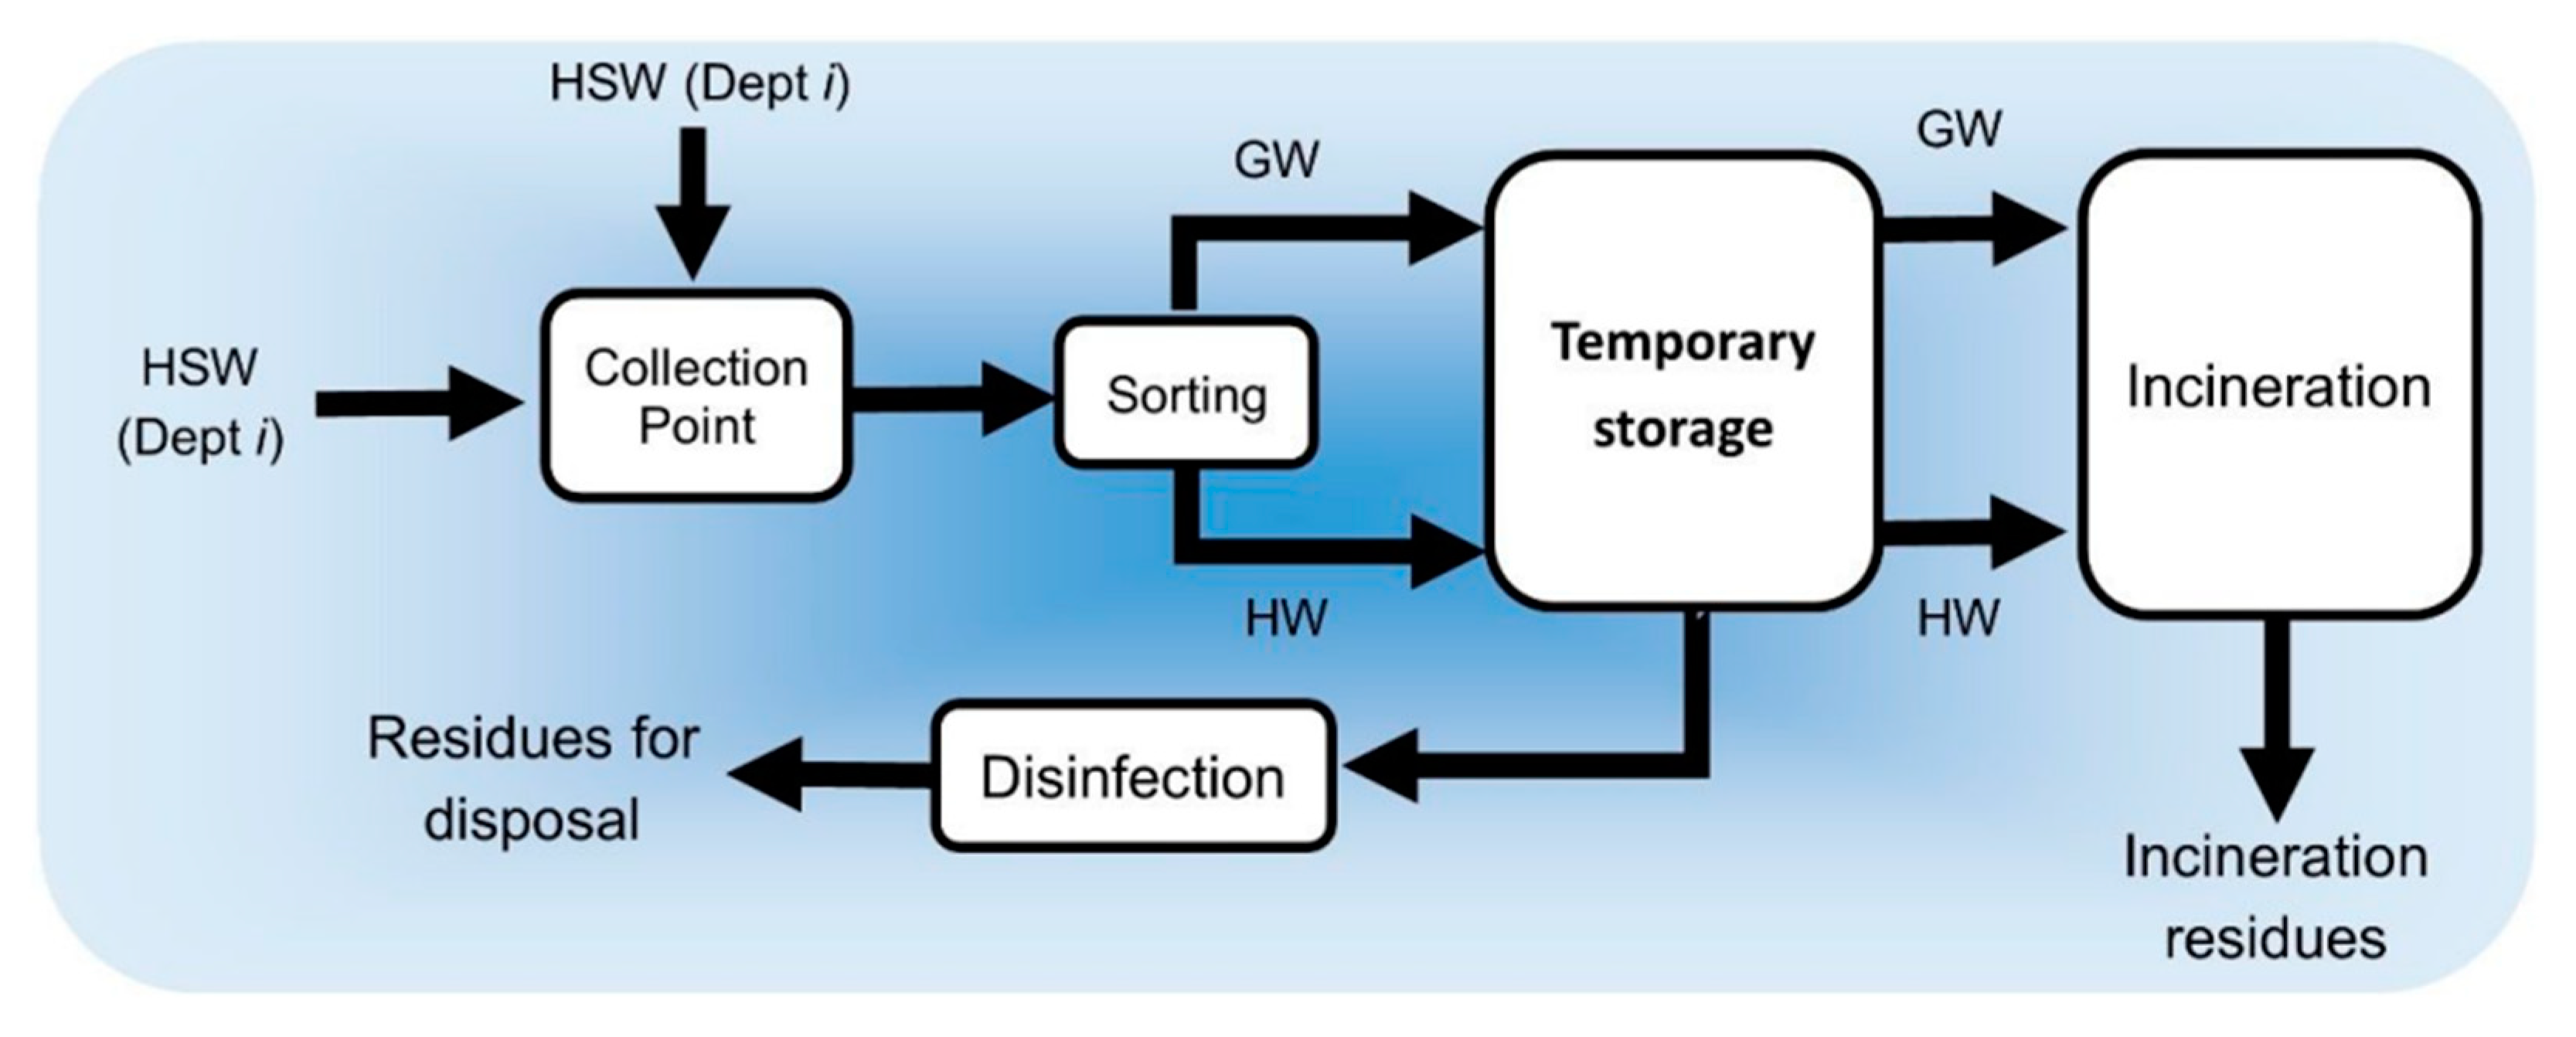
Scenario 2: During normal operation, all the H.S.W. generated in Hospital A is collected and sorted at the point of generation before being stored in a temporary storage facility in the hospital. The hazardous part of the H.S.W. will be transported to an off-site specialized incineration facility daily after over 12 h of storage in the temporary storage facility. The remaining non-hazardous waste will be chemically disinfected and disposed of as standard municipal solid waste (Figure 3). The chemical disinfection system used in the modeling process is the chemical disinfection system developed by ATHISA, Spain, and relevant data for this chemical disinfection system are described in the overview of technologies for the treatment of infectious and sharp waste from healthcare facilities [19]. During the emergency situation, all the H.S.W. (both hazardous and non-hazardous) from the infectious diseases department (collection point 4) is transported to an off-site specialized incineration facility daily after over 12 h of storage in the temporary storage facility. The rest of the H.S.W. from all other collection points will be treated similarly to the regular H.S.W. disposal procedure.
Figure 3.
H.S.W. disposal modeling scenario 2.
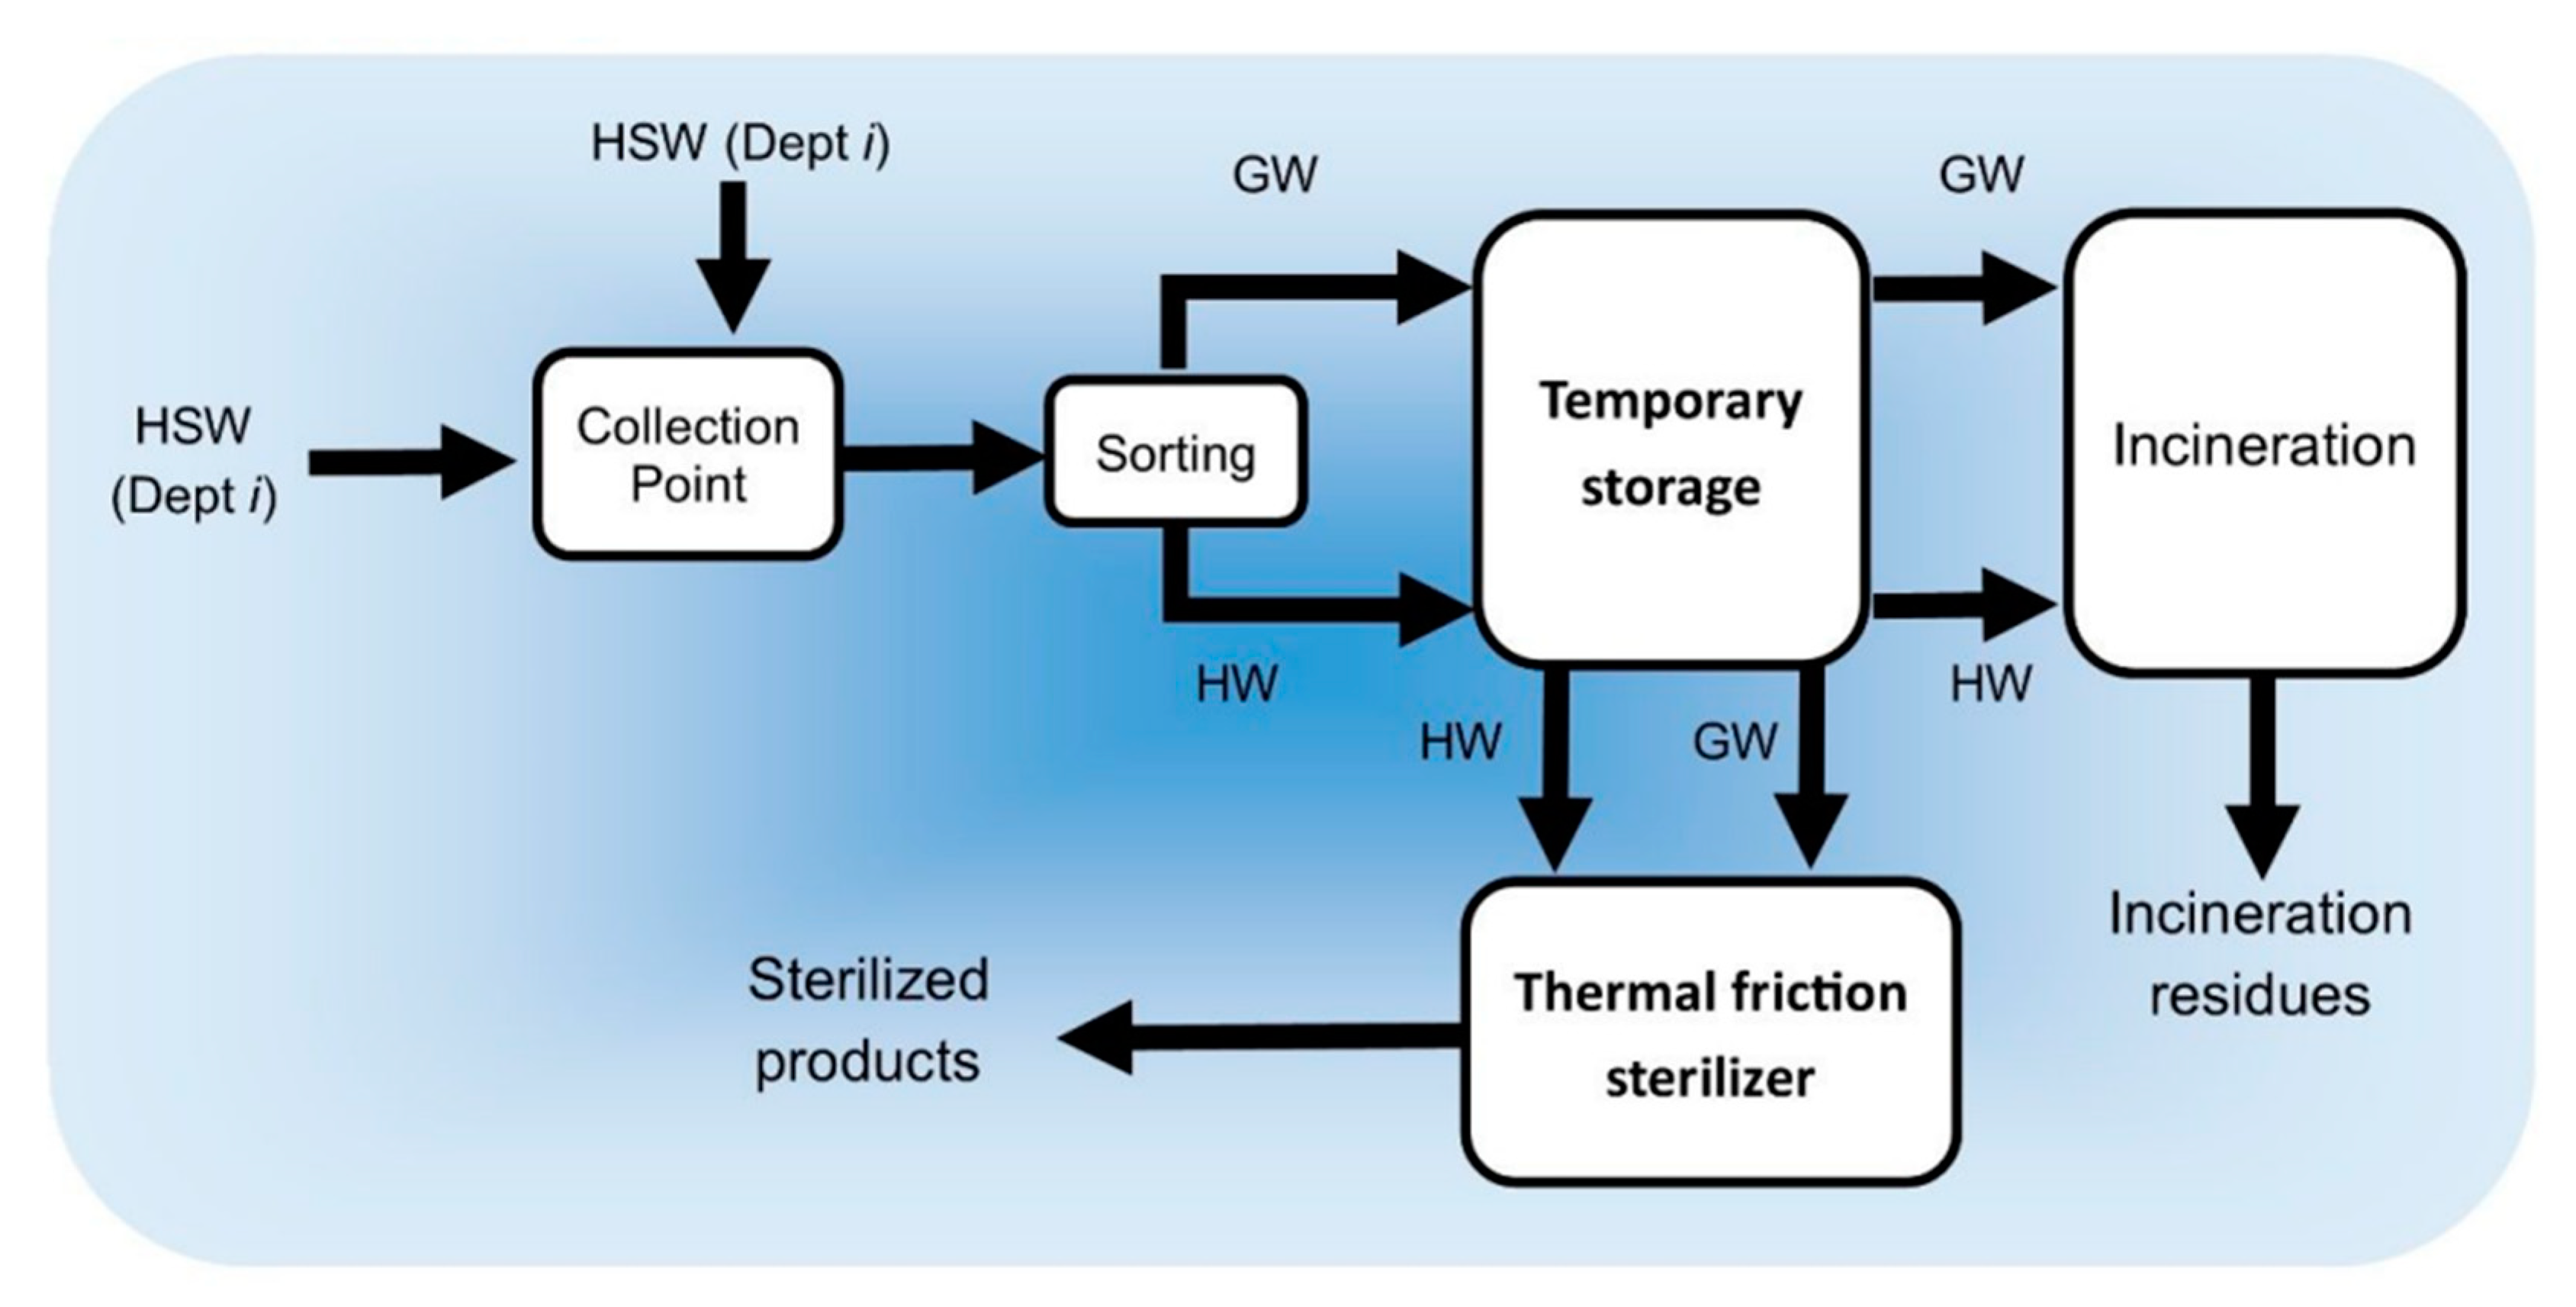
Scenario 3: All the H.S.W. generated in Hospital A is collected and sorted at the point of generation before being stored in a temporary storage facility in the hospital. Part of the hazardous waste in the H.S.W. is transported to an off-site specialized incineration facility daily after over 12 h of storage in the temporary storage facility. The remaining hazardous and non-hazardous waste will be treated using the thermal friction treatment system, and the products generated from the friction system are combustible waste (Figure 4). During the emergency situation, all the H.S.W. (both hazardous and non-hazardous) from the infectious diseases department (collection point 4) will be transported to an off-site specialized incineration facility daily after over 12 h of storage in the temporary storage facility. The rest of the H.S.W. from all other collection points will be treated similarly to the regular H.S.W. disposal procedure.
Figure 4.
H.S.W. disposal modeling scenario 3.
In this study, we assumed that the number of patients in the infectious diseases department (collection point 4) increased by 50~100% of the regular outpatient numbers. Additionally, research has shown that infectious diseases can trigger post-viral diseases [27,28,29]. We thus assumed that the H.S.W. generation rate in collection points 1, 2, 7, 10, and 11 increased by 5%. Additionally, the H.S.W. disinfected either through chemical disinfection and thermal frictional sterilization could contain moisture; thus, in this research, the threshold limit for moisture content in the end product was fixed to 20%.
2.3. Material and Energy Flow Characterization
Material flows analysis (M.F.A.), an approach used to quantify material flows within a system (such as H.S.W.), was conducted using STAN ver. 2.9.801 developed by Technische Universität Wien. The M.F.A. balance was based on the law of mass conservation. The modeling condition used in the M.F.A. analysis is shown in Table 3. There is a general classification of H.S.W. used in healthcare facilities, as described in Supplementary 1. As noted, for modeling purposes, we organized the H.S.W. either as hazardous H.S.W. (H.W.) or general H.S.W. (G.W.). In the material flow analysis, transportation was added as a process relevant to the modeling process, and encompassed handling and logistics.
Table 3.
The data of material flow analysis.
In the case of the H.S.W., the following formula is applicable [30,31].
where , and represent the gross material inflow, gross material outflow, and gross material stocks in the system, respectively. In the expression above, represents the gross material flow of H.S.W. generated at each collection point (. Additionally, for each scenario described before () could be expressed as follows:
Scenario 1:
Scenario 2:
Scenario 3:
In Equations (3) and (4), , and represent the residue from the incineration process, the H.S.W. disposed of in landfills after chemical disinfection, and calorific waste after thermal friction treatment process, respectively. Additionally, , and represent the equivalent mass flow of H.S.W. converted into exhaust gases and leachate during the temporary storage in the hospital, transportation, and disinfection processes, respectively. Generally, the medical waste is stored and transported at such temperatures (less than 5 °C), limiting the degradation process of H.S.W. [32]. Therefore, and will be negligible. Additionally, represents the material flow from the temporary storage facility. Since the accumulation of HSW-related waste is discouraged, stock accumulation was then neglected (). From Equations (2)–(4), and represent the equivalent mass flow of the H.S.W. converted to exhaust gases, steam/water, or leachate after the frictional treatment system. Thus, the and could be expressed as follows [17,18,19]:
In Equations (5) and (6) above, represents the H.S.W. flow (general and hazardous) transported to the incineration system. represents the H.S.W. flow (general and hazardous) from the temporary storage facility to the thermal frictional treatment system. The waste generation from each collection point was computed using the following formula:
In the formula above, corresponds to the number of patients per day and corresponds to the waste generation rate (kg person−1day−1).
3. Cost–Benefit Analysis
In the cost–benefit analysis, peoples’ preferences are not be discounted as a factor and thus neglected. Additionally, the costs of reducing air pollution were assumed to be part of the equipment maintenance costs, while the impacts of air emissions are omitted in the analysis. Therefore, the benefits accrued in the treatment process include the calorific value from the H.S.W. Although the incineration process is a source of thermal energy and electricity, H.S.W. incineration is more focused on the complete destruction of H.S.W. and less on energy recovery. For this reason, the benefits accrued from incineration will be negligible (. Chemical disinfection has negligible benefits and has more to do with costs: (). As for the thermal friction system, the residual product has a calorific value, and the benefits accrued ( will be computed using the following formula:
In the above equation, refers to the expected mass of the residual waste from the frictional treatment system, while refers to the market value of refuse-derived fuel in China. The overall costs of treating H.S.W. could be computed based on the set of equations proposed by Yu et al. [42]:
where , and represent the gross operational, investment, and disposal costs for each scenario, respectively. All the costs associated with temporary storage were neglected because we did not use storage conditions as a variable. The cost of disposal for each scenario could be computed as:
Scenario 1:
Scenario 2:
Scenario 3:
In Equations (10)–(12) above, represents the landfilling costs per tonne. Chemical disinfection equipment manufacturers have designed their equipment such that the disinfecting chemical solution is reduced to such conditions that could be treated in conventional wastewater treatment facilities, thus . The cost of investment could be computed as follows:
Scenario 1:
Scenario 2:
Scenario 3:
where ,, and represent the investment cost for the incineration equipment, disinfection equipment, thermal friction system per tonne of H.S.W., and the operation year, respectively. The operational costs could be computed by Formulas (16)–(18), and the variables definition and costs are derived in Table 4.
Table 4.
Variables and cost in the cost–benefit analysis.
Scenario 1:
Scenario 2:
Scenario 3:
Additionally, solid waste treatment processes are associated with costs and unusable products. However, we observed that some of the resources used in the H.S.W. processes could be recovered for other purposes. Thus, we analyzed the modeling results based on the capacity to recover resources for further use (i.e., resources conversion factor) and the following expressions apply:
Scenario 1:
Scenario 2:
Scenario 3:
4. Results and Discussion
4.1. MFA Analysis Results
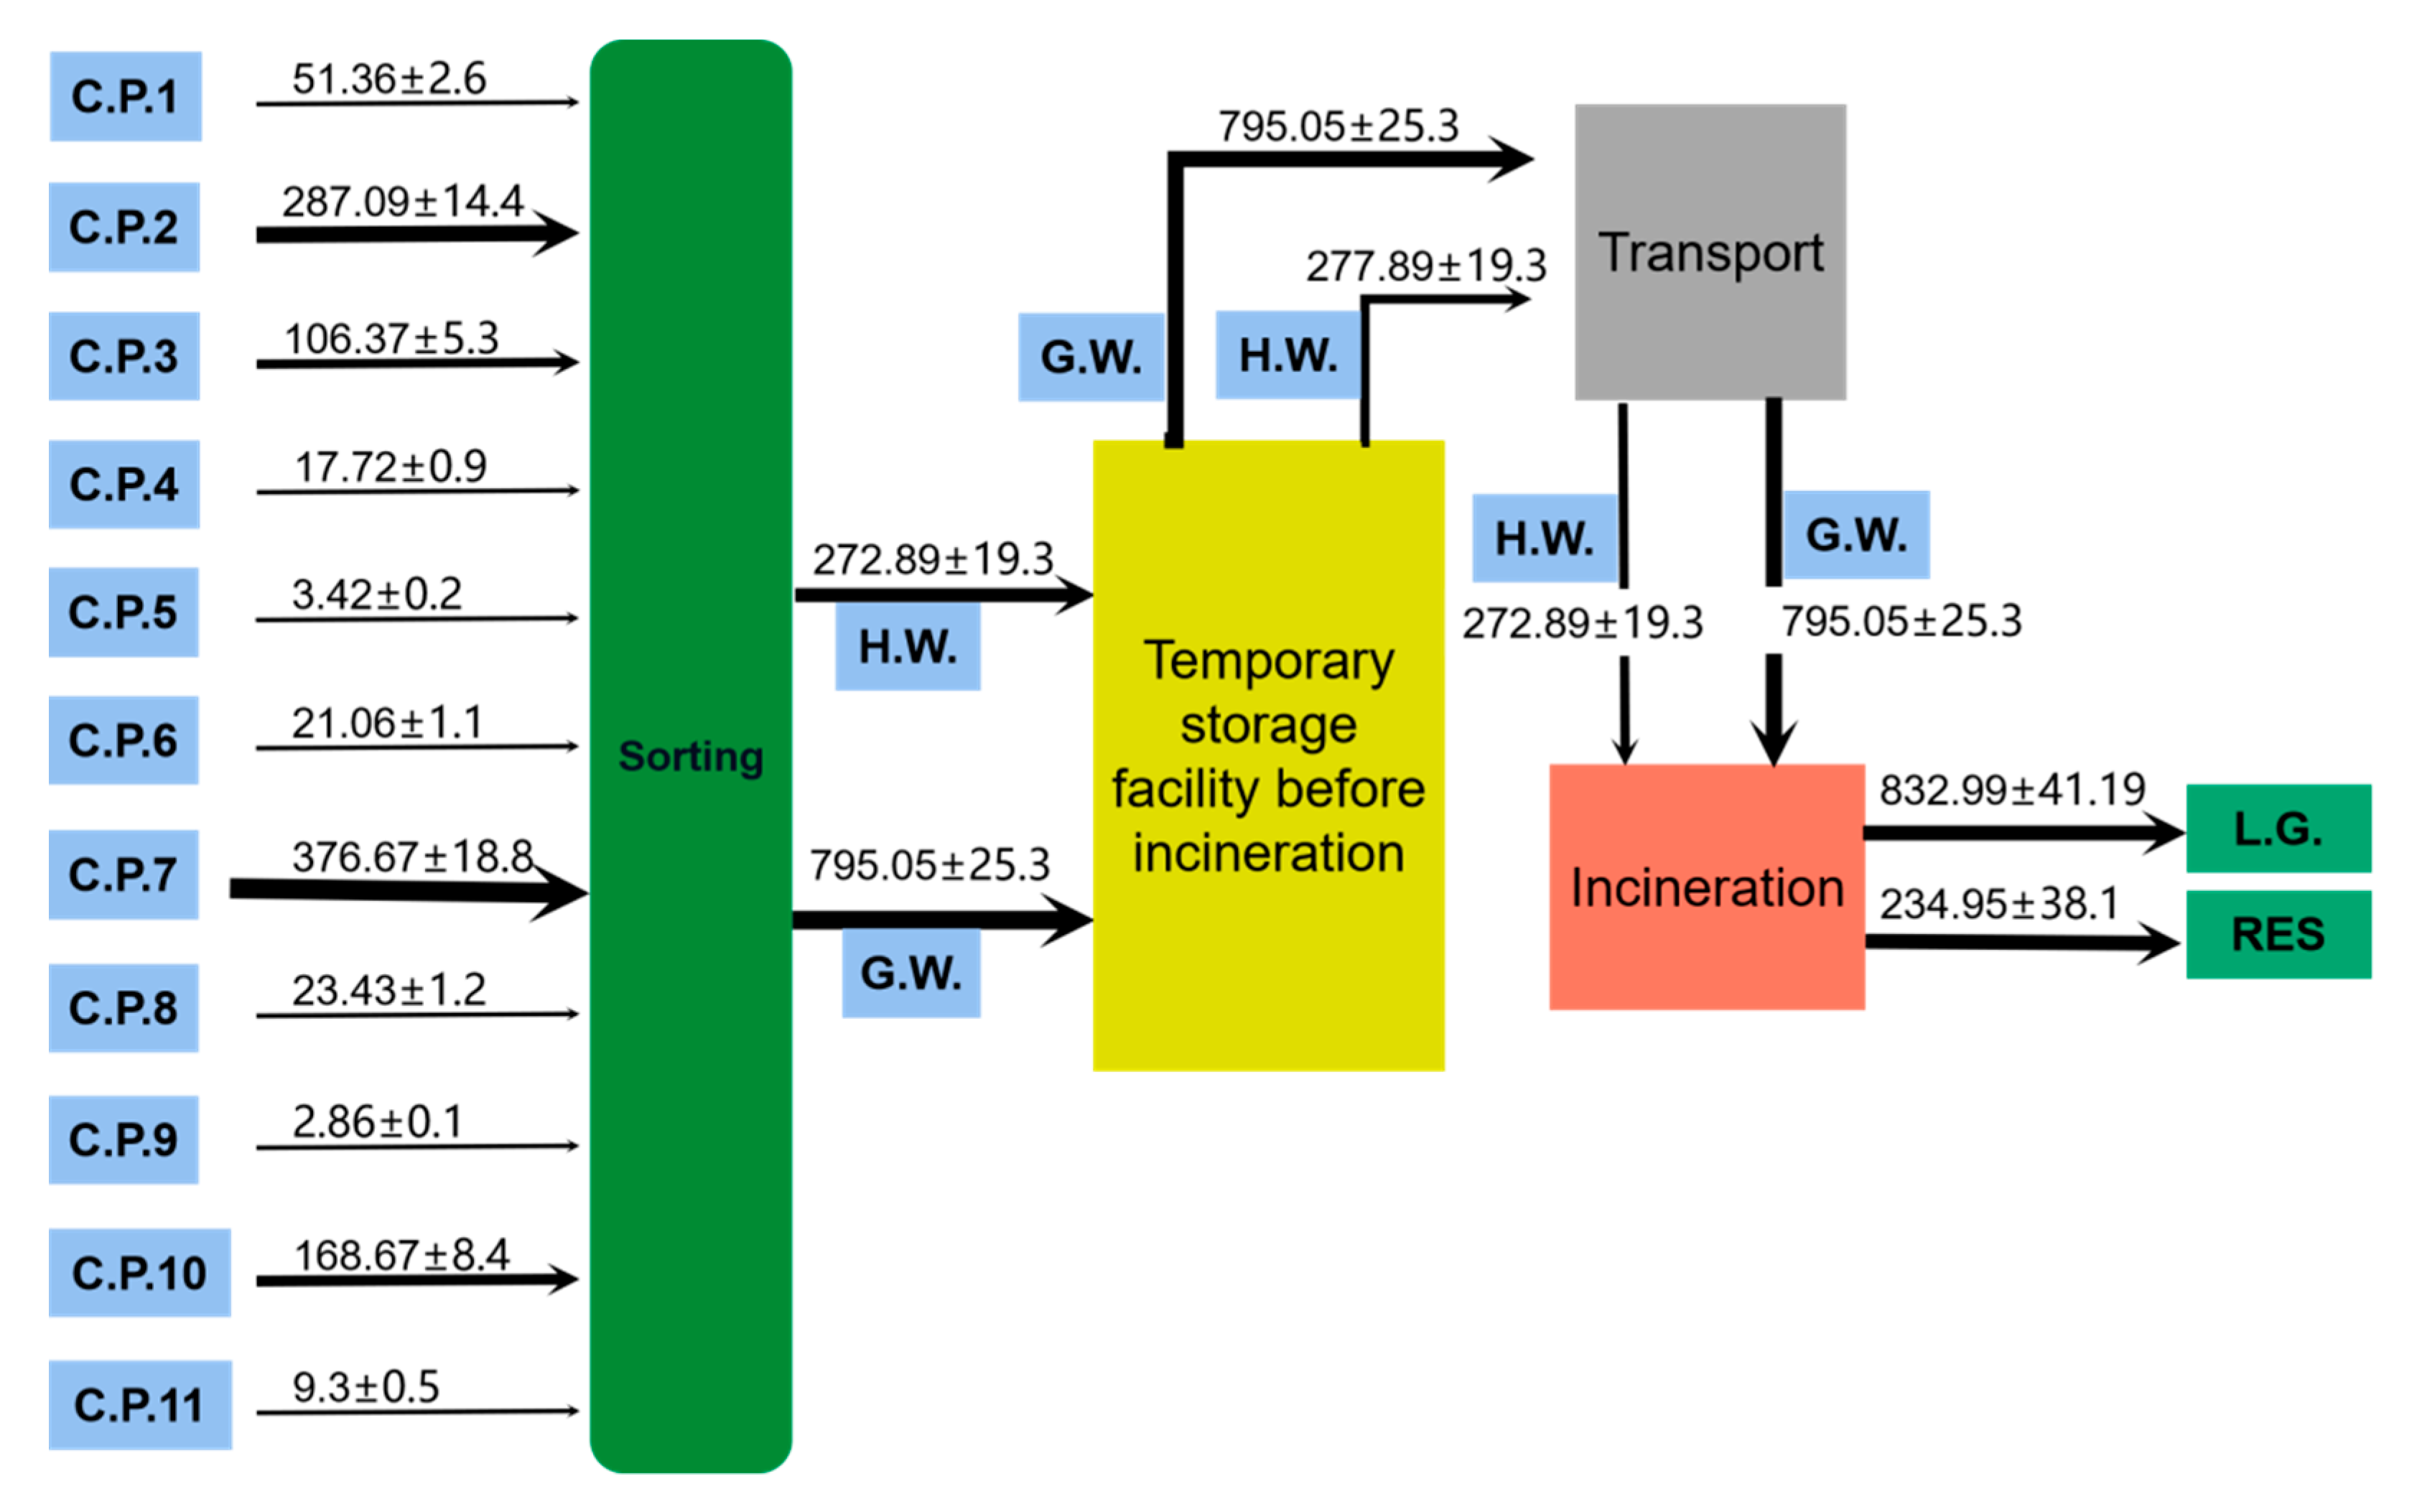
An average H.S.W. of 1344.68 kg day−1 would be generated daily and incinerated during normal operating conditions when scenario 1 is considered. During the incineration process, approximately 22% (approximately 297.66 kg day−1) of the incinerated H.S.W. would be collected as slag/fly ash () for landfill. The M.F.A. modeling results show that approximately 26% of the waste is hazardous while the rest of the H.S.W. waste is general H.S.W. The representative Sankey diagrams and M.F.A. analysis results are shown in Figure 5 and Table 5.
Figure 5.
The Sankey diagrams for scenario 1.
Table 5.
M.F.A. analysis results for scenario 1.
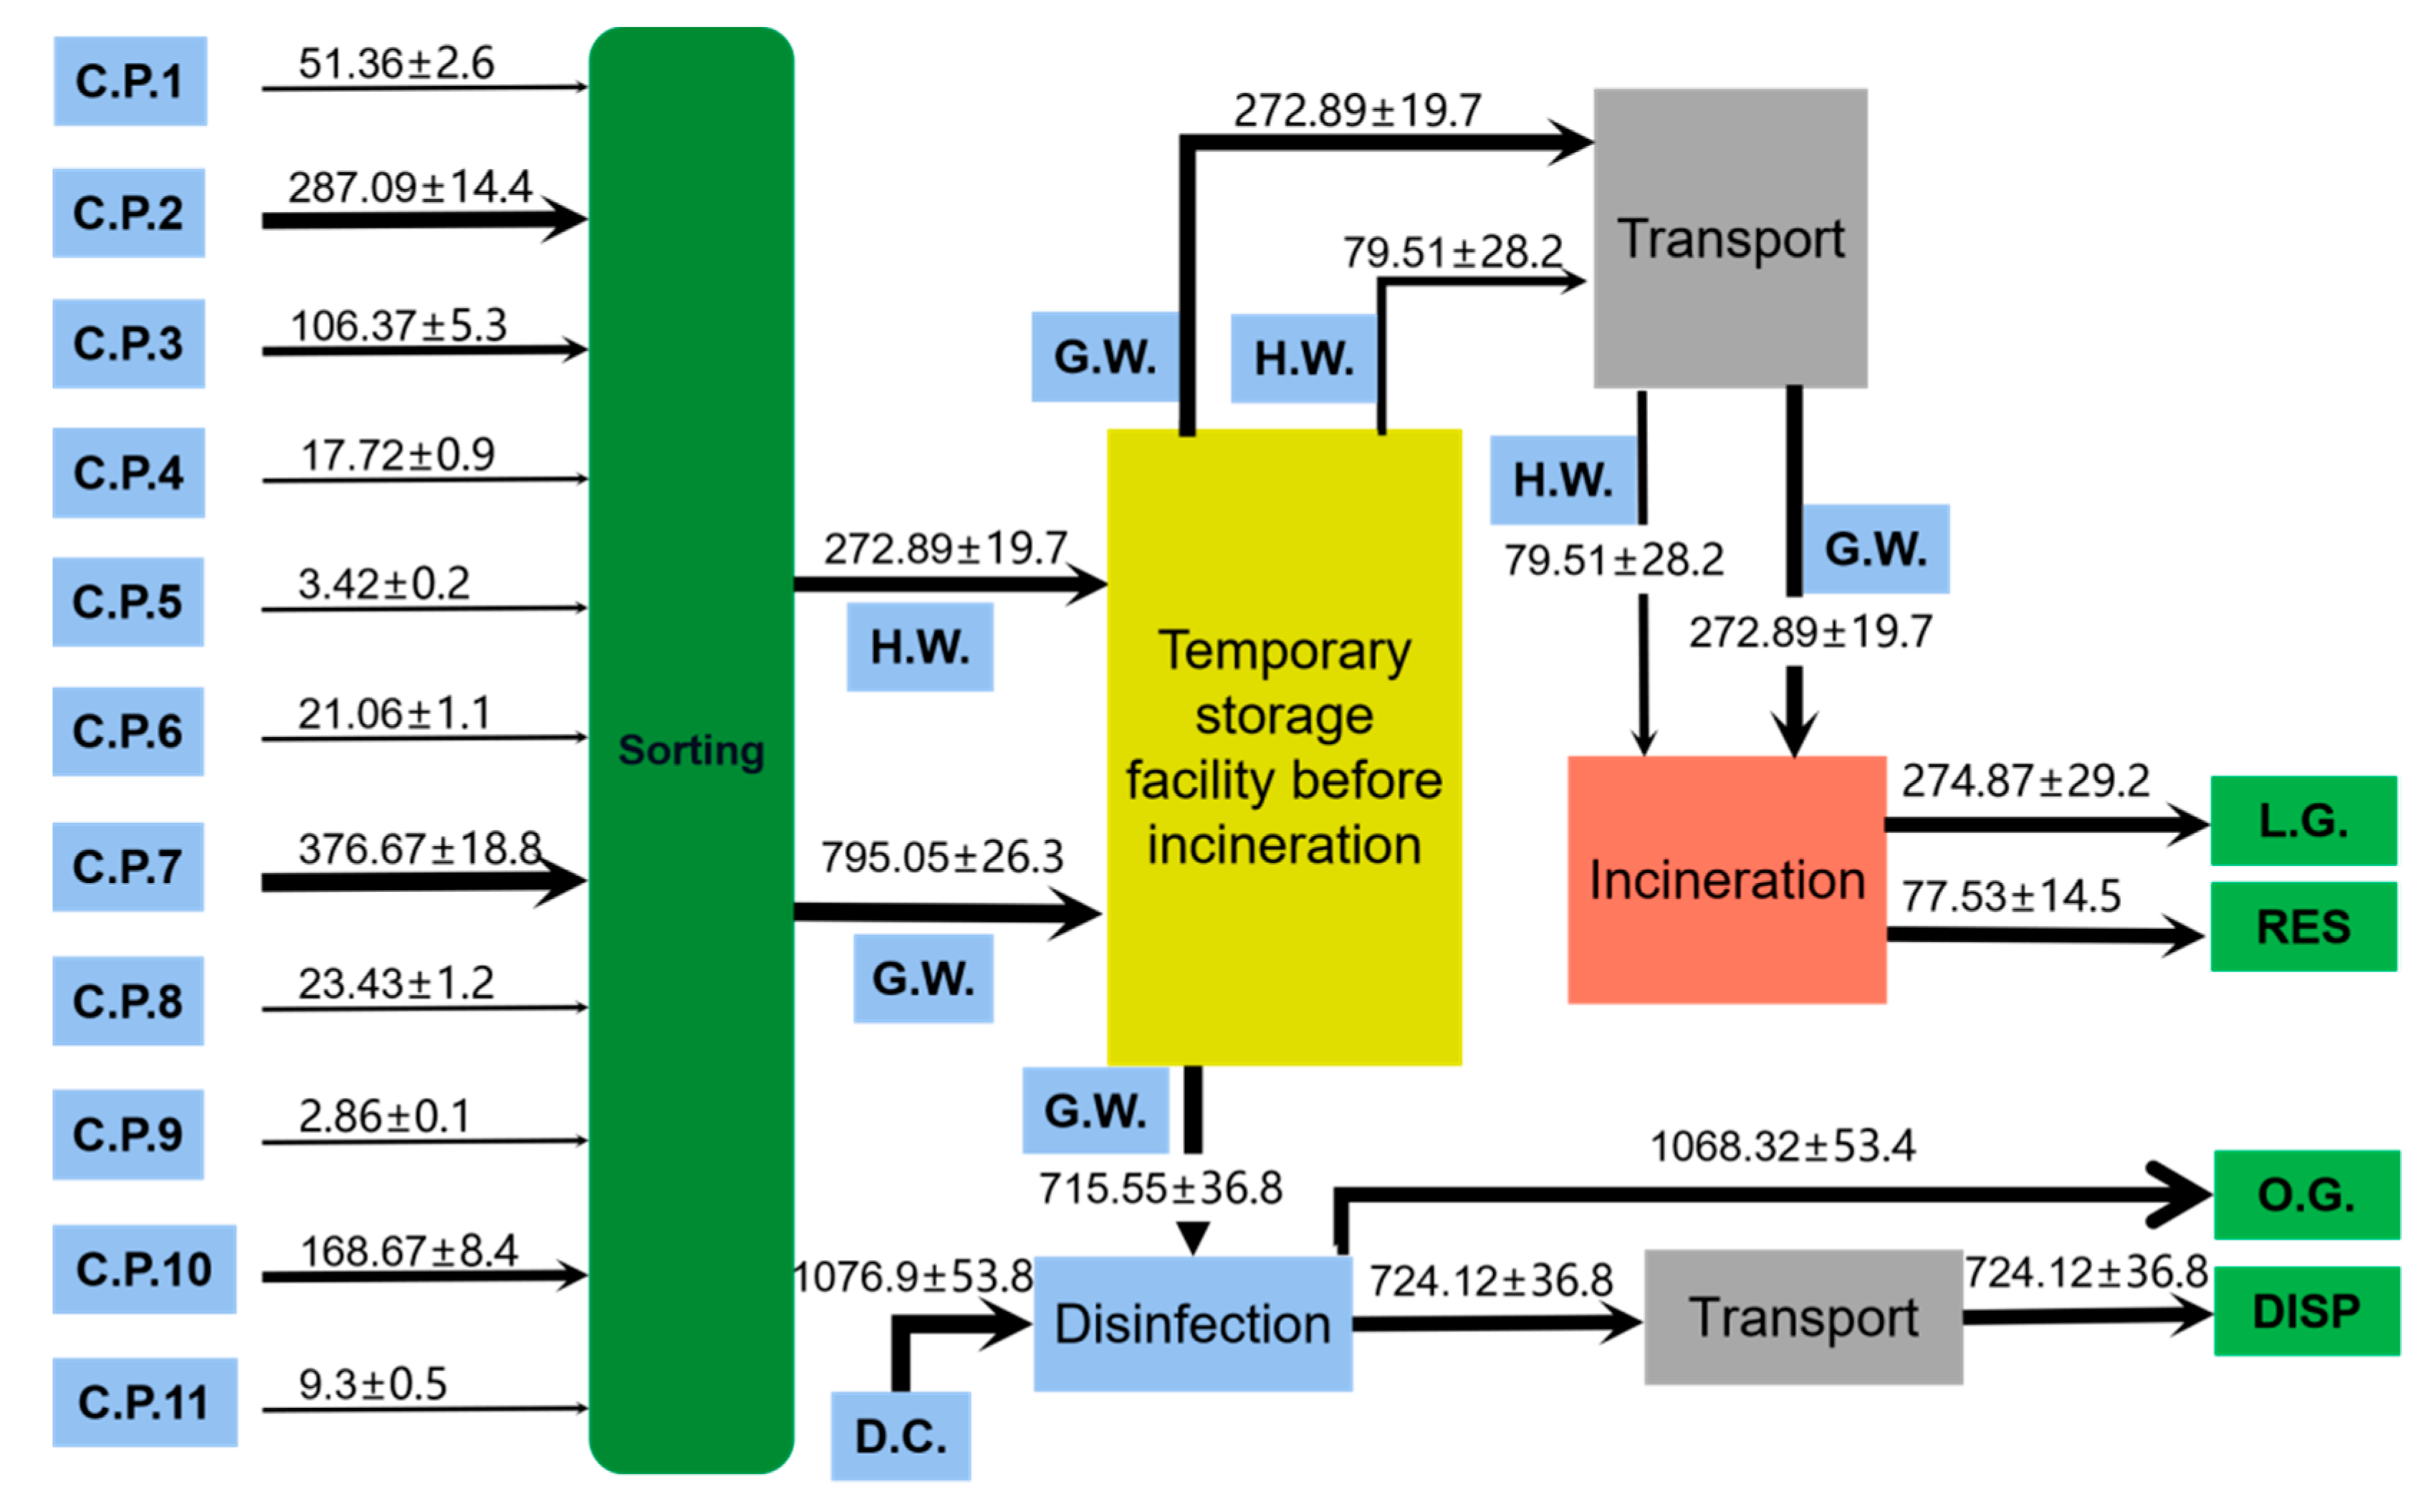
During normal operating conditions, a similar quantity of H.S.W. waste coupled with disinfection chemicals and water would be treated in scenario 2(). Approximately 1361.58 L day−1 of disinfection chemical solution is required for chemical disinfection and consists of 904.67 L day−1 water and 456.91 L day−1 disinfecting chemical solution. Approximately 66.7% of the total generated H.S.W. is treated through the chemical disinfection process, of which 954.10 kg day−1 and 1171.94 kg day−1 disinfected H.S.W. is generated in modeling scenarios 2(1) and 2(2), respectively. The difference in the quantity is due to the possibility (proposed in Table 5) that the disposable waste could retain moisture content after the disinfection process. In modeling scenario 2, approximately 33% (450.57 kg day−1) of the total H.S.W. is incinerated and generates 99.13 kg day−1 slag/fly ash. The dominant component subjected to the incineration process in this scenario is the hazardous H.S.W. The representative Sankey diagrams and M.F.A. analysis results are shown in Figure 6 and Table 6.
Figure 6.
The Sankey diagrams for scenario 2.
Table 6.
M.F.A. analysis results for scenario 2.
Modeling scenario 3 focuses on reducing the “harmful” slag/fly ash generated during the incineration process. Thus, approximately 31–50% of the total H.S.W. generated could be incinerated from the M.F.A. modeling results, thereby rendering 22% slag for all the case studies in modeling scenario 3, i.e., 3(1), 3(2) and 3(3).
On the other hand, 50–69% of the total generated H.S.W.—if sterilized using a thermal frictional sterilization system—would be reduced by 25%. This means that a 75% dry fraction of the calorific sterilized products would be generated. Alternatively, approximately 105% of the H.S.W. sterilized using the thermal frictional sterilization system would be generated if the sterilized product contains a moisture content. Then, 1–1.4 m3 of water would be used and 0.99–1.64 m3 discharged to the sewer for municipal treatment. As mentioned in the previous section and in prior observations, the 0.99 m3 would be discharged because the caloric end product of the thermal frictional sterilization system would have a moisture content. The representative Sankey diagrams and M.F.A. analysis results are shown in Figure 7 and Table 7.
Figure 7.
The Sankey diagrams for scenario 3.
Table 7.
M.F.A. analysis results for scenarios 3.
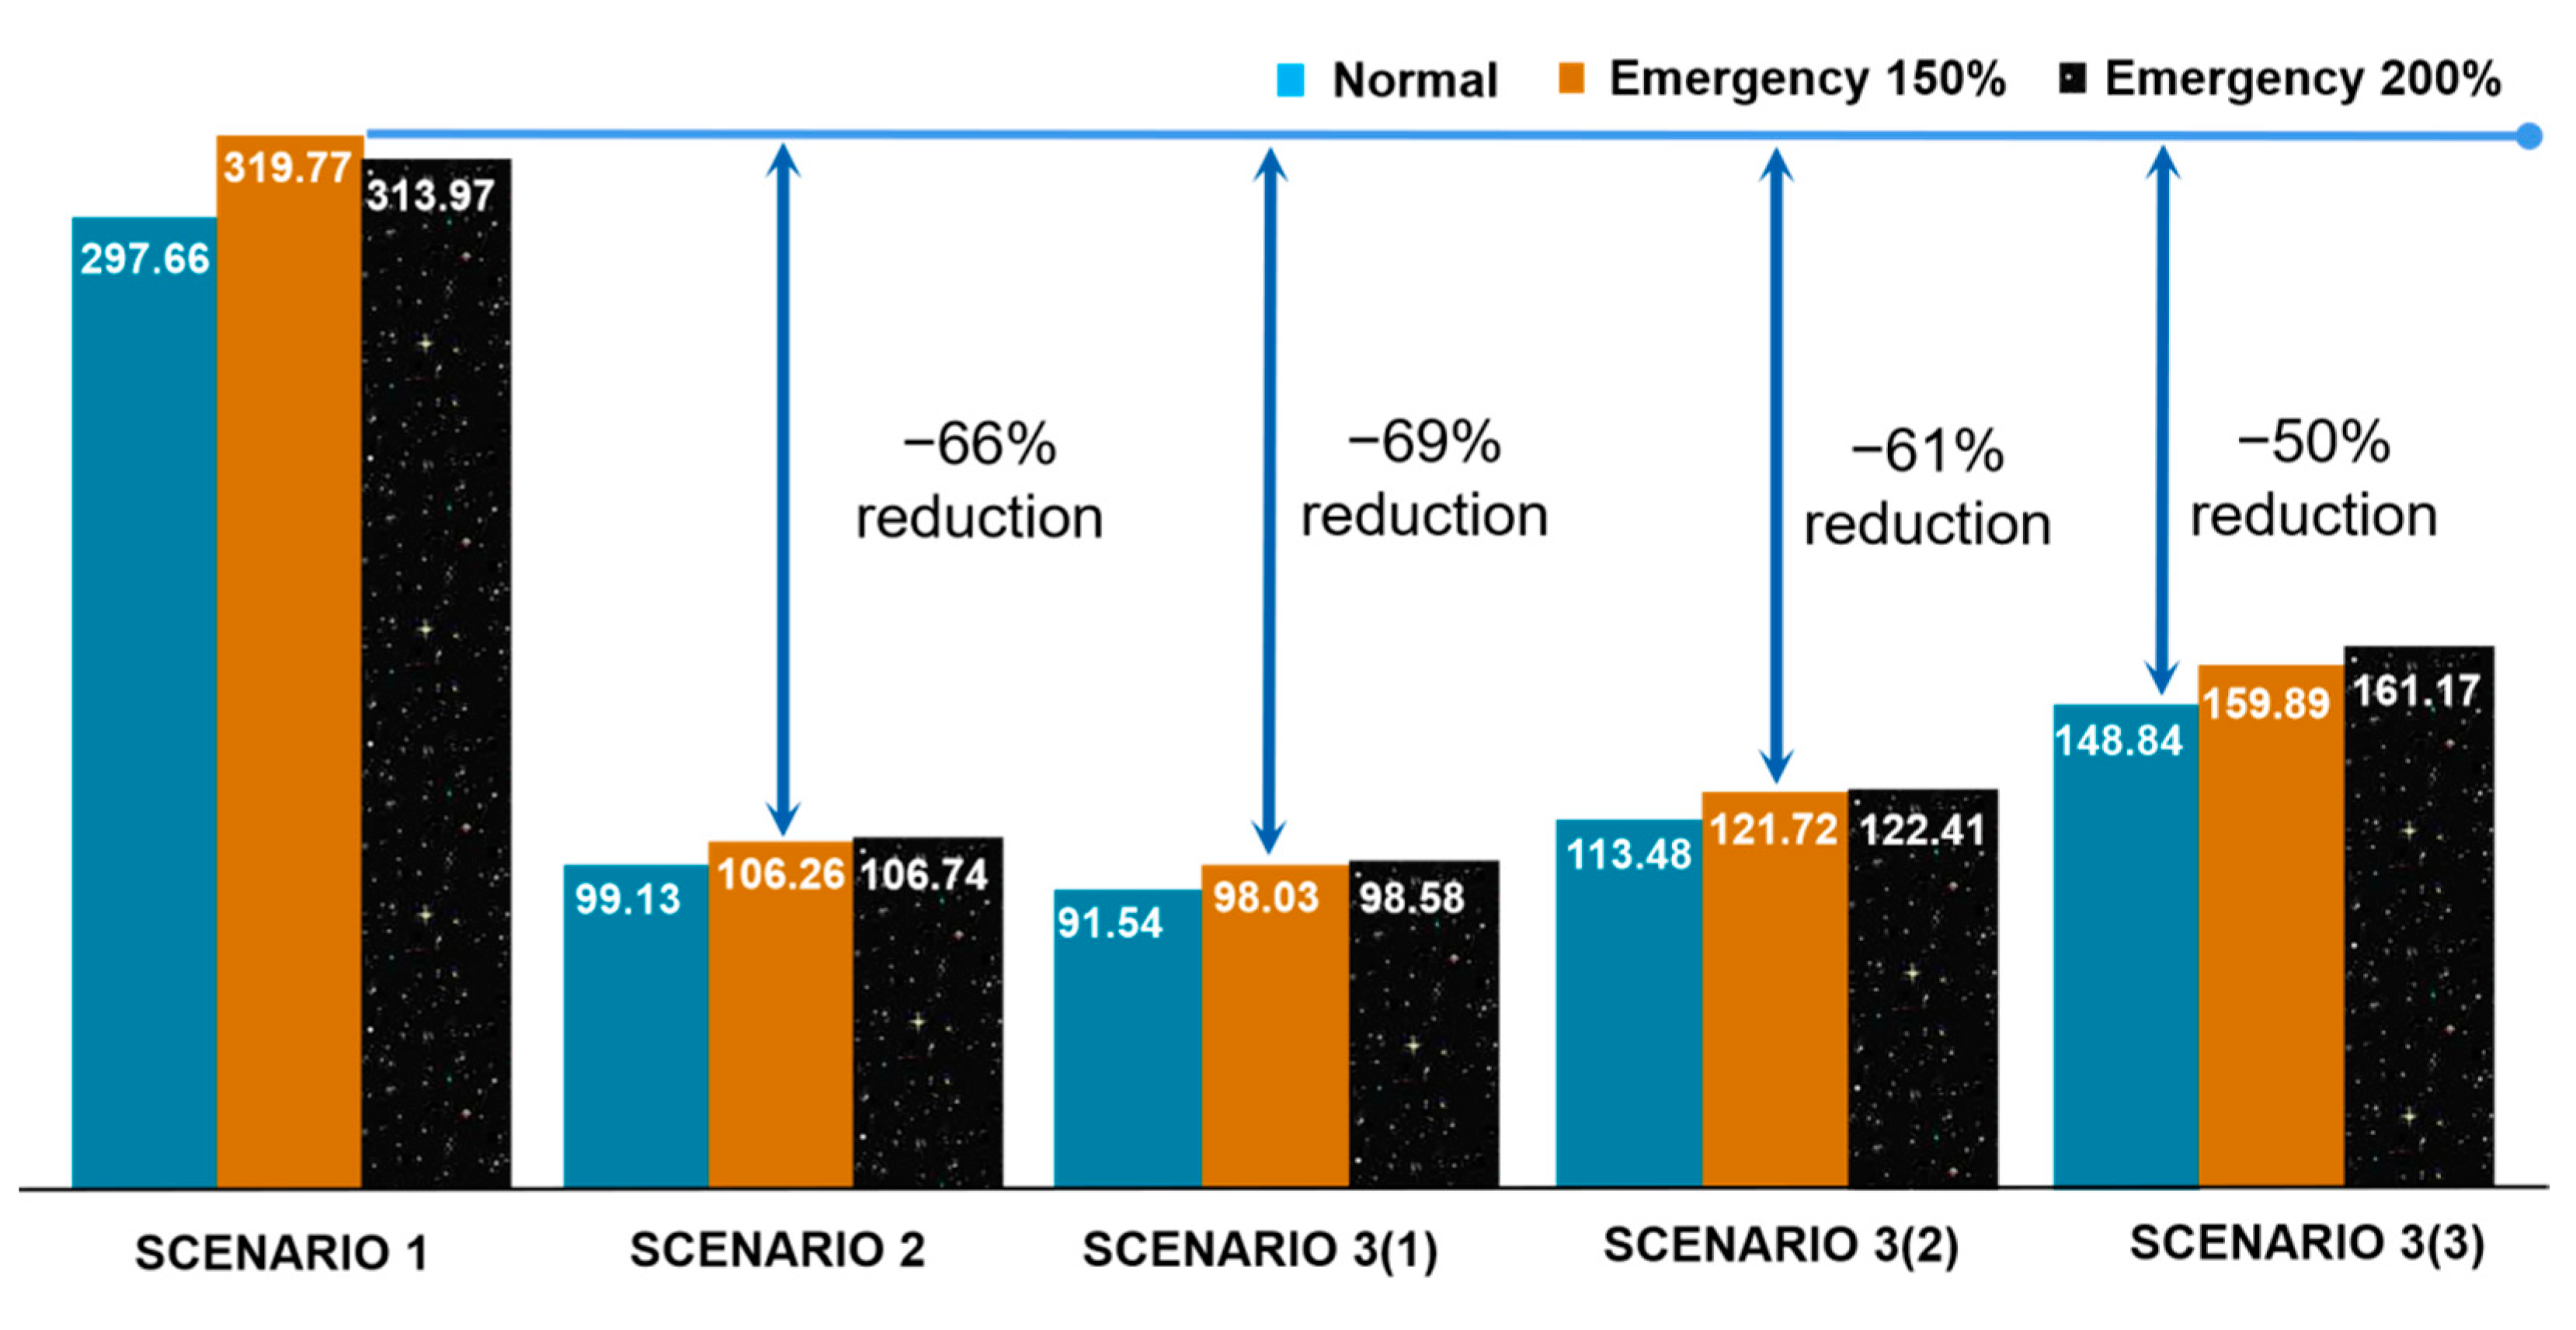
During normal operating conditions, the quantity of slag/fly ash to be landfilled in modeling scenarios 2 and 3 is reduced by 66.7% and 50–69.3%, respectively, relatively to scenario 1 (Figure 8). For modeling scenario 3, a higher H.S.W. diversion rate using the TFS integrated system will reduce the quantity of fly ash/slag to be landfilled. This means that such a system will be much more sustainable than the conventional stand-alone systems used in healthcare facilities (Figure 8). Furthermore, society at large will be able to benefit from less fly ash/slag being generated and the need to create an additional footprint for landfill.
Figure 8.
Comparative analysis of the three modeling scenarios.
However, if we consider the total quantity of H.S.W. to be landfilled (R.E.S. and DISP), modeling scenario 2 will generate the highest quantity relative to modeling scenarios 1 and 3. The reason would be that most of the combustible H.S.W. treated using the chemical disinfection process (assuming minimum loss) would be landfilled.
4.2. Cost–Benefit Analysis
During normal operation, modeling scenario 3 would reduce the overall H.S.W. treatment costs by 61.2% compared to scenario 1 if the hazardous H.S.W. and the total H.S.W. from collection point 4 alone were to be incinerated. Such savings would result from introducing the “recovery” unit, i.e., the thermal frictional sterilization equipment. Thus, a gradual increase in the general H.S.W. to be incinerated would reduce the economic benefits (relative to scenario 1) from 61.2% to 43.5%. On the contrary, modeling scenario 3 would have tangible economic benefits compared to modeling scenario 2 if the hazardous H.S.W. and total H.S.W. from collection point 4 alone were to be incinerated. The gradual increase in the general H.S.W. to be incinerated (compared to modeling scenario 3 case studies 3(2) and 3(3)) would require more treatment costs. The possible reason for such an observation could be that the chemical disinfection system is limited to the treatment of the general H.S.W. Therefore, scenario 3 has more flexibility in terms of H.S.W. treatment and the composition of H.S.W. to be treated, and exhibited better economic benefits relative to scenarios 2 and 1. The cost–benefit analysis results are shown in Table 8.
Table 8.
Cost–benefit analysis results.
During emergency operating conditions, when 150% of H.S.W. is generated at collection point 4, approximately 55–61% of H.S.W. treatment costs would be reduced if scenario 3 were effected and not the current system, i.e., scenario 1. The incineration system would be used to treat H.S.W. from collection point 4 (i.e., infectious diseases, etc.), while the rest of the H.S.W. would be treated and A calorific end product recovered: in this manner, the incineration process will be decongested. When the H.S.W. generated at collection point 4 increases by 200%, 44–54% savings would be achieved compared to the current treatment system. Therefore, hospital A could save money through the selective incineration of hazardous and infectious waste, leaving the remaining H.S.W. to be treated and end products recovered using the TFS system. A previously described comparative analysis between scenarios 2 and 3 ( during normal operation) also applies to the emergency operating conditions. As mentioned in the introduction and in this section, the thermal frictional sterilization units could be a sort of “recovery” unit that reduces H.S.W. costs and recovers the calorific end product which could be used as a source of energy.
Of particular interest is the fact that the operating costs accrued from all the treatment scenarios form the most significant part of the costs. In scenario 1, the operational costs are approximately 97% of the total costs of treating H.S.W. per day because of the sanitary transportation costs from the storage site to specialized incineration facility. In scenarios 2 and 3, the operational costs account for 94–96%. A detailed look at the results shows that the bulk of the operating costs is from the sanitary transportation costs from the storage site to the specialized incineration facility—thereby reducing the quantity of the H.S.W. to be incinerated. Therefore, during difficult times such as when a pandemic hits, the incineration process could be used to treat specific H.S.W., leaving the remaining H.S.W. to be treated with the thermal frictional sterilization system.
Considering the benefits accrued from the perspective of recovering resources, scenario 3 would have the best indices relative to modeling scenarios 1 and 2: this trend is observed during normal and emergency operating conditions (Table 9). The positive indices of modeling scenario 3 could be because of the calorific end product generated and water recovery from the process. Furthermore, we assume that part of the H.S.W. subjected to the thermal frictional sterilization process will be converted into steam (and finally condensate) which could be removed together with the sterilizing water. Therefore, the wastewater could be reused if an adequate water purification system is installed. During normal operation conditions, the resources conversion factor order is scenario 3 > modeling scenario 1 > modeling scenario 2. Modeling scenario 2 exhibits a resources recovery factor of −0.24 mainly because the disinfected end product is landfilled. Thus, if the sterilized end product contains moisture content, then the resources conversion factor would be −0.74, which is way worse than the initial condition (no moisture content). On the contrary, the resources conversion factor for modeling scenario 3 would increase from 1.7 to 1.8 when the calorific end product contains moisture content. Therefore, modeling scenario 2 could have tangible economic benefits with a negative resource conversion factor. The incineration would be a costly treatment process with a lesser negative resource conversion factor as compared to modeling scenario 2.
Table 9.
Mean resources conversion factor.
5. Conclusions
This research investigated the benefits accrued from integrating different H.S.W. treatment systems with the existing incineration system. The following conclusions were drawn from the modeling process:
- Approximately 26% of the total H.S.W. generated from H.S.W. is hazardous—the remaining H.S.W. is general H.S.W.
- A chemical disinfection system would disinfect 66.7% of the total H.S.W. and reduce the incinerable H.S.W. to 33.3%.
- Hospital A would save approximately 58% if an integrated chemical disinfection-incineration treatment system was implemented relative to the current stand-alone incineration system. The economic savings could be from the reduction in sanitary transportation costs.
- The thermal frictional sterilization system would be an effective way of decongesting the incineration system and handle 50–70% of the total H.S.W.
- Hospital A would save approximately 43–61% if an integrated thermal frictional sterilization–incineration treatment system was implemented relative to the current stand-alone incineration system. The economic savings could be from reducing sanitary transportation costs and the minimal benefits from the calorific end product from the frictional sterilization system.
- Scenario 3 provides the optimal treatment mode in terms of resource recovery. The resource conversion factor during normal and emergency situations is in the order of scenario 3 > scenario 1 > scenario 2.
From the modeling results, integrated model scenario 3 would be the appropriate integration model for Hospital A during normal and emergency operating conditions. Furthermore, the thermal frictional sterilization system could be used as a recovery unit for the calorific end product, and the system could use a variable composition of the H.S.W. This modeling study was limited to the economic benefits. Further studies related to environmental cost–benefit analysis were not conducted because of insufficient knowledge of the physicochemical processes. It is essential to broaden this research to include the environmental impacts of H.S.W. treatment processes.
Author Contributions
Conceptualization, methodology, writing—original draft preparation, C.Y. and A.M.N.; software, A.M.N.; validation, formal analysis, C.Y., L.Y. and J.J.; investigation, J.J.; data curation, W.W. and J.L.; writing—review and editing, visualization, J.J., W.W. and J.L.; supervision, L.Y. and A.M.N.; project administration, resources, C.Y. and A.M.N. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by the study of comprehensive treatment and countermeasures support fund (Grant No: BK202012) in close collaboration with the R&D team of Silla Entech Co., Ltd.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data used to support the analysis of this study are available from the corresponding author upon request.
Acknowledgments
We are grateful for the support and contribution of the R&D team of Silla Entech Co., Ltd.
Conflicts of Interest
The authors declare no conflict of interest.
References
- The Hindu. Medical Waste Found Dumped in Vacant Land at Chettipalayam. 2022. Available online: https://www.thehindu.com/news/cities/Coimbatore/medical-waste-found-dumped-in-vacant-land-at-chettipalayam/article36934945.ece (accessed on 15 August 2022).
- Thakur, V.; Sharma, S. Assessment of healthcare solid waste management practices for environmental performance: A study of hospitals in Himachal Pradesh, India. Manag. Environ. Qual. An Int. J. 2021, 32, 612–630. [Google Scholar] [CrossRef] [Scilit]
- Gai, R.; Kuroiwa, C.; Xu, L.; Wang, X.; Zhang, Y.; Li, H.; Zhou, C.; He, J.; Tang, W.; Kuroiwa, C.; et al. Hospital medical waste management in Shandong Province, China. Waste Manag. Res. 2009, 27, 336–342. [Google Scholar] [CrossRef] [Scilit]
- Su, M.; Wang, Q.; Li, R. How to dispose of medical waste caused by COVID-19? A case study of China. Int. J. Environ. Res. Public Health 2021, 18, 12127. [Google Scholar] [CrossRef] [Scilit]
- Tsai, W.T. Analysis of medical waste management and impact analysis of COVID-19 on its generation in Taiwan. Waste Manag. Res. 2021, 39, 27–33. [Google Scholar] [CrossRef] [Scilit]
- Wyssusek, K.H.; Keys, M.T.; van Zundert, A.A.J. Operating room greening initiatives–the old, the new, and the way forward: A narrative review. Waste Manag. Res. 2018, 37, 3–19. [Google Scholar] [CrossRef] [Scilit]
- Lu, C.; Liu, Q.; Zhang, B.; Yin, L. A pareto-based hybrid iterated greedy algorithm for energy-efficient scheduling of distributed hybrid flowshop. Expert Syst. Appl. 2022, 204, 117555. [Google Scholar] [CrossRef] [Scilit]
- Deepak, A.; Kumar, D.; Sharma, V. Developing an effectiveness index for biomedical waste management in Indian states using a composite indicators approach. Environ. Sci. Pollut. Res 2021, 28, 64014–64029. [Google Scholar] [CrossRef] [Scilit]
- Ranjbari, M.; Shams Esfandabadi, Z.; Shevchenko, T.; Chassagnon-Haned, N.; Peng, W.; Tabatabaei, M.; Aghbashlo, M. Mapping healthcare waste management research: Past evolution, current challenges, and future perspectives towards a circular economy transition. J. Hazard. Mater. 2022, 422, 126724. [Google Scholar] [CrossRef] [Scilit]
- Peng, Y.; Wu, P.; Schartup, A.T.; Zhang, Y. Plastic waste release caused by COVID-19 and its fate in the global ocean. Proc. Natl. Acad. Sci. USA 2021, 118, e2111530118. [Google Scholar] [CrossRef] [Scilit]
- Valizadeh, J.; Hafezalkotob, A.; Seyed Alizadeh, S.M.; Mozafari, P. Hazardous infectious waste collection and government aid distribution during COVID-19: A robust mathematical leader-follower model approach. Sustain. Cities Soc. 2021, 69, 102814. [Google Scholar] [CrossRef] [Scilit]
- Al-Khatib, I.A.; Al-Qaroot, Y.S.; Ali-Shtayeh, M.S. Management of healthcare waste in circumstances of limited resources: A case study in the hospitals of Nablus city, Palestine. Waste Manag. Res. 2009, 27, 305–312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tudor, T.L.; Townend, W.K.; Cheeseman, C.R.; Edgar, J.E. An overview of arisings and large-scale treatment technologies for healthcare waste in the United Kingdom. Waste Manag. Res. 2009, 27, 374–383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Love, E. Z.W.E. Finds Sorroundings of Waste Incinerators Are “Highly” Contaminated. Resource 2022. Available online: https://resource.co/article/zwe-finds-surroundingswaste-incinerators-are-highly-contaminated?utm_source=Newsletter+Signups+from+Website&utm_campaign=7643f95714-EMAIL_CAMPAIGN_2020_10_09_09_44_COPY_02&utm_medium=email&utm_term=0_01e1502761-7643f95714-560 (accessed on 15 August 2022).
- Makajic-Nikolic, D.; Petrovic, N.; Belic, A.; Rokvic, M.; Radakovic, J.A.; Tubic, V. The fault tree analysis of infectious medical waste management. J. Clean. Prod. 2016, 113, 365–373. [Google Scholar] [CrossRef] [Scilit]
- Shi, J.; William, Z. Coronavirus: China Struggling to Deal with Mountain of Medical Waste Created by Epidemic, South China Morning Post. 2020. Available online: https://www.scmp.com/news/china/society/article/3065049/coronavirus-china-struggling-deal-mountain-medical-waste-created (accessed on 15 August 2022).
- NewsterGroup. Sterilizer for Hospital Solid Waste N.W. 2022. Available online: https://www.newstergroup.com/hospital-solid-waste/37/sterilizer-nw5 (accessed on 15 August 2022).
- UNEP. Compendium of Technologies for Treatment/Destruction of Healthcare Waste; International Environmental Technology Centre, Division of Technology, Industry and Economics, United Nations Environment Programme: Osaka, Japan, 2012. [Google Scholar]
- WHO. Overview of Technologies for the Treatment of Infectious and Sharp Waste from Health Care Facilities; WHO: Geneva, Switzerland, 2019. [Google Scholar]
- Giakoumakis, G.; Politi, D.; Sidiras, D. Medical Waste Treatment Technologies for Energy, Fuels, and Materials Production: A Review. Energies 2021, 14, 8065. [Google Scholar] [CrossRef] [Scilit]
- Mwaria, P.R.; Kaseva, M.E.; Manyele, S.V. Characterization of healthcare waste in Tanzanian zonal referral hospitals as a key factor for energy recovery. Afr. J. Environ. Sci. Technol. 2021, 15, 349–365. [Google Scholar] [CrossRef] [Scilit]
- Atkinson, G.; Braathen, N.A.; Groom, B.; Mourato, S. Cost-Benefit Analysis and the Environment: Further Development and Policy Use; OECD Publishing: Paris, France, 2018. [Google Scholar]
- Adhikari, S.R.; Supakankunit, S. Benefits and costs of alternative healthcare waste management: An example of the largest hospital of Nepal. WHO South-East Asia J. Public Health 2014, 3, 171–178. [Google Scholar] [CrossRef] [Scilit]
- Files, A.C.; Allen, T.G.; Criner, G.K. Least-Cost Options for the Collection, Treatment, and Disposal of Biomedical Waste in Maine. MAFES Tech. Bull. 2002, 184, 1–20. [Google Scholar]
- Rashidian, A.; Alinia, C.; Majdzadeh, R. Cost-effectiveness analysis of health care waste treatment facilities in iran hospitals; a provider perspective. Iran. J. Public Health 2015, 44, 352–360. [Google Scholar]
- Khashij, M.; Pakdaman, M.; Mehralian, M.; Abtahi, M.; Mokhtari, M. Cost-Effectiveness Analysis of Infectious Waste Treatment Devices in Hospital. J. Environ. Health Sustain. Dev. 2018, 3, 645–649. [Google Scholar] [CrossRef] [Scilit]
- Daugherty, S.E.; Guo, Y.; Heath, K.; Dasmariñas, M.C.; Jubilo, K.G.; Samranvedhya, J.; Lipsitch, M.; Cohen, K. Risk of clinical sequelae after the acute phase of SARS-CoV-2 infection: Retrospective cohort study. BMJ 2021, 373, n1098. [Google Scholar] [CrossRef] [Scilit]
- Lopez-Leon, S.; Wegman-Ostrosky, T.; Perelman, C.; Sepulveda, R.; Rebolledo, P.A.; Cuapio, A.; Villapol, S. More than 50 long-term effects of COVID-19: A systematic review and meta-analysis. Sci. Rep. 2021, 11, 16144. [Google Scholar] [CrossRef] [Scilit]
- Smatti, M.K.; Cyprian, F.S.; Nasrallah, G.K.; Al Thani, A.A.; Almishal, R.O.; Yassine, H.M. Viruses and Autoimmunity: A Review on the Potential Interaction and Molecular Mechanisms. Viruses 2019, 11, 762. [Google Scholar] [CrossRef] [Scilit]
- Olatayo, K.I.; Mativenga, P.T.; Marnewick, A.L. COVID-19 PPE plastic material flows and waste management: Quantification and implications for South Africa. Sci. Total Environ. 2021, 790, 148190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yin, L.; Li, X.; Lu, C.; Gao, L. Energy-Efficient Scheduling Problem Using an Effective Hybrid Multi-Objective Evolutionary Algorithm. Sustainability 2016, 8, 1268. [Google Scholar] [CrossRef] [Scilit]
- Taslimi, M.; Batta, R.; Kwon, C. Medical Waste Collection Considering Transportation and Storage Risk. Comput. Oper. Res. 2020, 120, 104966. [Google Scholar] [CrossRef] [Scilit]
- Altin, S.; Altin, A.; Elevli, B.; Cerit, O. Determination of hospital waste composition and disposal methods: A case study. Pol. J. Environ. Stud. 2003, 12, 251. [Google Scholar]
- Komilis, D.; Fouki, A.; Papadopoulos, D. Hazardous medical waste generation rates of different categories of health-care facilities. Waste Manag. 2012, 32, 1434. [Google Scholar] [CrossRef] [Scilit]
- Cheng, Y.W.; Sung, F.C.; Yang, Y.; Lo, Y.H.; Chung, Y.T.; Li, K.C. Medical waste production at hospitals and associated factors. Waste Manag. 2009, 29, 440. [Google Scholar] [CrossRef] [Scilit]
- Hoenich, N.A.; Levin, R.; Pearce, C. Clinical waste generation from renal units: Implications and solutions. Semin. Dial. 2005, 18, 396. [Google Scholar] [CrossRef] [Scilit]
- Hsu, S.; Thiel, C.; Mello, M.J.; Slutzman, J.E. Dumpster diving in the emergency department: Quantity and characteristics of waste at a Level I trauma center. West. J. Emerg. Med. Integr. Emerg. Care Popul. Health 2020, 21, 1211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komilis, D.; Makroleivaditis, N.; Nikolakopoulou, E. Generation and composition of medical wastes from private medical microbiology laboratories. Waste Manag. 2017, 61, 539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mandalidis, A.; Topalidis, A.; Voudrias, E.A.; Iosifidis, N. Composition, production rate and characterization of Greek dental solid waste. Waste Manag. 2018, 75, 124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mihai, F.C. Assessment of COVID-19 waste flows during the emergency state in Romania and related public health and environmental concerns. Int. J. Environ. Res. Public Health 2020, 17, 5439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Namburar, S.; Pillai, M.; Varghese, G.; Thiel, C.; Robin, A.L. Waste generated during glaucoma surgery: A comparison of two global facilities. Am. J. Ophthalmol. 2018, 12, 87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, S.; Dong, H. Uncover cost-benefit disparity of municipal solid waste incineration in Chinese Provinces. Sustainability 2020, 12, 697. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).