


Abstract
Background/Objectives: Beta-thalassemia (β-thal) is an inherited hemoglobin disorder caused by mutations in the HBB gene. Hb Malay (HBB:c.59A>G [NM_000518.5], p.Asn20Ser, CD19), a missense substitution (AAC→AGC; Asn→Ser) in exon 1 of the β-globin gene causing β+-thalassemia, has been mainly described in Southeast Asian populations but remains underreported in published Indonesian molecular epidemiology literature. This study aimed to identify the Hb Malay variant and investigate its familial segregation in a large Indonesian extended family. Methods: Cascade molecular screening was initiated following detection of the mutation in a proband referred for genetic testing. Sixteen individuals (one proband and 15 family members) consented to participate. Genomic DNA was extracted from peripheral blood and a 1.9-kb β-globin gene fragment was amplified by PCR. Mutation screening was performed using the Thalassemia GenoArray Kit HBGA-THAL-b31 (Hybribio) and confirmed by Sanger sequencing. A three-generation pedigree was constructed from molecular results and family interviews. Results: The Hb Malay mutation (HBB:c.59A>G) was identified in 13 of 16 individuals: 12 heterozygous carriers (A/G) and one homozygous individual (G/G, subject III-1, aged 15 years). Three individuals showed the normal genotype (A/A). Pedigree analysis demonstrated autosomal recessive inheritance across three generations. No α-globin deletions covered by the GenoArray panel were detected. Conclusions: To our knowledge, this is one of the few documented reports of cascade molecular screening for the Hb Malay (HBB:c.59A>G) variant in a large extended Indonesian family, confirmed by dual molecular methods. These findings illustrate the potential value of cascade molecular screening for early carrier identification in settings where hemoglobin fractionation testing is unavailable, and highlight the need for population-based epidemiological studies to guide thalassemia prevention policy in Indonesia.
1. Introduction
β-Thalassemia (β-thal) is one of the most common inherited hemoglobin disorders worldwide, caused by mutations in the HBB gene that lead to reduced or absent production of β-globin chains. The clinical manifestations range from mild anemia in carriers to severe transfusion-dependent conditions in individuals with β-thal major [1,2,3]. Indonesia has one of the highest numbers of thalassemia cases in Southeast Asia, with an estimated 3–10% of the population being carriers and over 10,000 registered cases of thalassemia major [4,5,6].
β-Thal arises from over 300 different mutations in the HBB gene, broadly categorized into β0-thal (complete absence of β-globin synthesis) and β+-thal (reduced but not absent synthesis). One such variant occurs at codon 19 of the β-globin gene, known as hemoglobin Malay (Hb Malay; HBB:c.59A>G), also referred to as β-thal CD19. This missense substitution replaces asparagine (AAC) with serine (AGC), resulting in β+-thalassemia. Hb Malay has been frequently reported in Malaysia [7,8,9,10,11,12,13,14] and Thailand [15]. While Hb Malay is rarely reported in published Indonesian molecular epidemiology studies, which have predominantly focused on more common mutations such as IVS-1–5 (G>C), CD26 (HbE), and CD41/42 (−TTCT) [16,17], its carrier frequency among South Sumatran Malay populations has been reported at approximately 5.3% [18], suggesting the variant may be underdetected rather than truly uncommon in this ethnic group. The underrepresentation of Hb Malay in the literature may partly reflect the reliance on standard mutation panels that do not include CD19 in routine screening.
When β-thal is discovered in a large family, it raises important concerns about the inheritance pattern and health risks for family members, requiring cascade screening and genetic counselling [19,20,21]. This study aimed to identify the β-thal CD19 variant in an extended family using molecular techniques, to construct a three-generation pedigree, and to highlight the importance of molecular screening for early carrier identification.
2. Detailed Case Description
The index case (proband, III-2) is a 15-year-old female who was initially identified during a school-based anemia screening program. Laboratory findings revealed a hemoglobin (Hb) level of 9.3 g/dL and a mean corpuscular volume (MCV) of 80.5 fL, indicating mild anemia with a near-normal MCV. It should be noted that a near-normal MCV (80.5 fL) is atypical for classic heterozygous β-thalassemia, which commonly presents with MCV below 80 fL and elevated HbA2. As HbA2 quantification and iron studies (serum ferritin, serum iron, TIBC) were unavailable at the study site (see below), co-existing iron-deficiency anemia, highly prevalent among Indonesian adolescent females, cannot be excluded as a contributing cause of the observed anemia. This hematological profile nonetheless prompted referral to our molecular diagnostic laboratory for further evaluation.
A relevant family history was noted: the proband’s mother (II-4, 46 years old) had previously been diagnosed with thalassemia-associated anemia at another laboratory, but the specific mutation type and subtype had not been disclosed to her at the time of diagnosis. This reflects a broader challenge in Indonesia, where thalassemia remains underrecognized and underdiagnosed in clinical practice, largely overshadowed by the more commonly suspected iron-deficiency anemia. Consequently, many carriers and affected individuals remain unaware of their precise genetic status and the hereditary implications for their families.
Capillary hemoglobin electrophoresis was not available at the study site; therefore, HbA2 quantification could not be performed. Molecular screening using the Thalassemia GenoArray Kit HBGA-THAL-b31 (Hybribio) identified the Hb Malay variant (HBB:c.59A>G [NM_000518.5], p.Asn20Ser) in the proband in the heterozygous state (A/G genotype), subsequently confirmed by Sanger sequencing.
Following detection of the Hb Malay variant in the proband, the extended family expressed interest in determining their carrier status. A total of 16 individuals across three generations (including the proband) voluntarily submitted peripheral blood samples for molecular analysis. All participants provided written informed consent (or parental consent for minors) specifically for molecular testing. No additional clinical examination or complete hematological profiling was performed, as participants consented exclusively to molecular genetic screening. The family was originally from South Sumatra and had relocated to Jakarta, a region where the Hb Malay variant is known to be prevalent among the Malay ethnic population [18]. Following disclosure of results, all family members were provided with information on the hereditary nature of β-thalassemia and the importance of genetic counseling, particularly for those of reproductive age and for the homozygous individual (III-1, aged 15 years).
3. Materials and Methods
3.1. Subjects and Ethical Approval
One patient (proband, III-2) with clinical suspicion of thalassemia initiated this study. After detection of the Hb Malay variant, cascade screening was extended to 15 additional consenting family members, for a total of 16 individuals across three generations. The study was approved by the Ethics Committee of the Faculty of Medicine, UIN Syarif Hidayatullah Jakarta (No. B-019/F12/KEPK/TL.00/08/2025), and conducted in accordance with the Declaration of Helsinki. Written informed consent was obtained from all participants or their legal guardians.
3.2. DNA Extraction and PCR Amplification
Genomic DNA was extracted from peripheral blood using the gSYNC™ DNA Extraction Kit (Geneaid Biotech Ltd., New Taipei City, Taiwan) per manufacturer’s instructions. A 1.9-kb segment of the β-globin gene was amplified by PCR using forward primer 5′-AGTAGCAATTTGTACTGATGGTATGG-3′ and reverse primer 5′-TTTCCCAAGGTTTGAACTAGCTCTT-3′. PCR conditions: initial denaturation 94 °C/3 min; 35 cycles of 94 °C/40 s, 62 °C/30 s, 72 °C/1 min; final extension 72 °C/2 min. Products were verified by agarose gel electrophoresis [22,23].
3.3. Mutation Screening Using GenoArray
The Thalassemia GenoArray Kit HBGA-THAL-b31 (Guangdong Hybribio Biotech Co., Ltd. yang berlokasi di Chaozhou, China) was used for simultaneous detection of β-globin mutations and α-globin deletions via flow-through hybridization. The kit comprises two membranes: (1) HybriMem THAL b23 SEA, detecting 23 β-globin point mutations and small deletions: −50 (C>G), −31 (A>G), −28 (A>G), −86 (C>G), −90 (C>T), CD8/9 (+G), CD15 (G>A), CD17 (A>T), CD19 (A>G) [Hb Malay], CD26 (G>A) [HbE/βE], CD27–28 (+C), CD35 (A>T), CD41 (−T), CD41–42 (−TTCT), CD43 (G>T), CD71–72 (+A), CD95 (+A), CD123–125 (del AGT), CD126 (C>T), IVS-I-1 (G>T), IVS-I-5 (G>C), IVS-II-654 (C>T), and Del619 (619 bp deletion); and (2) HybriMem THAL b8 SEA, detecting 7 α-globin large deletions: −−SEA, −α3.7, −−FIL, −−SIRI, −−THAI, −HPFH-6, −−LEP, and 1 b-globin large deletion (Del619). Samples were processed per manufacturer’s instructions using the HybriMax flow-through hybridization device. Mutations and deletions outside the scope of this panel were not assessed in this study.
3.4. DNA Sequencing and Data Analysis
All GenoArray-positive samples for β-thal CD19 were confirmed by Sanger sequencing (Apical Scientific Sdn. Bhd., Petaling Jaya, Malaysia). Chromatograms were analyzed using ApE (A Plasmid Editor) version v3.1.8.1 software.
3.5. HGVS Nomenclature
The mutation is designated HBB:c.59A>G (reference transcript NM_000518.5), resulting in the amino acid change p.Asn20Ser at the protein level. The designation ‘codon 19’ as used in earlier literature refers to the mature β-globin chain numbering system, which omits the initiator methionine residue; in standard HGVS coding sequence numbering, this corresponds to position 20 (c.59A>G). Both designations are used in this report to facilitate cross-referencing with the existing literature.
3.6. Pedigree Analysis
A three-generation pedigree was constructed based on molecular results and structured interviews with the proband and available family members to illustrate the distribution and segregation of the variant within the family.
4. Results
4.1. Molecular Analysis Overview
As described in the Case Presentation, the proband (III-2) presented with a hemoglobin level of 9.3 g/dL and MCV of 80.5 fL. The remaining 15 family members underwent molecular analysis only, as they consented exclusively to genetic screening without additional hematological profiling. Capillary hemoglobin electrophoresis was unavailable at the study site; therefore, HbA2 levels could not be determined. GenoArray screening followed by Sanger sequencing allowed accurate identification of the HBB:c.59A>G (NM_000518.5) variant and demonstrated its segregation within this extended family.
4.2. Pedigree and Genotypic Distribution
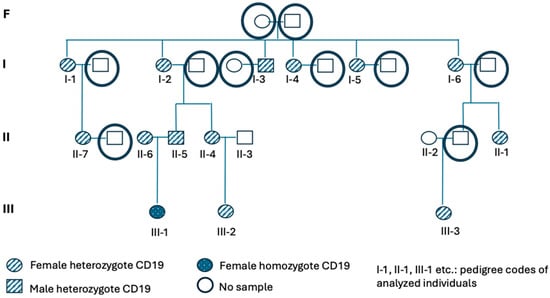
The segregation pattern of the Hb Malay variant is shown in Figure 1. A total of 16 individuals from three generations (I, II, III) were analyzed. The genotypic distribution is summarized in Table 1, demonstrating normal (A/A), heterozygous carrier (A/G), and homozygous for the Hb Malay variant (G/G) genotypes within the family.
Figure 1.
Pedigree of the extended family showing segregation of the Hb Malay (HBB:c.59A>G) variant. Squares represent males; circles represent females. Open symbols: normal genotype (A/A); half-filled symbols: heterozygous carriers (A/G); filled symbols: homozygous for the Hb Malay variant (G/G). Numbers denote individuals whose samples were analyzed; alphabetical codes represent family members without samples. square refer to male, circle refer to female.
Table 1.
Genotypic distribution of the Hb Malay (HBB:c.59A>G) variant among analyzed family members.
4.3. Sanger Sequencing Confirmation
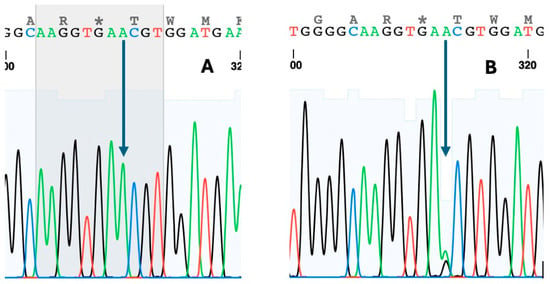
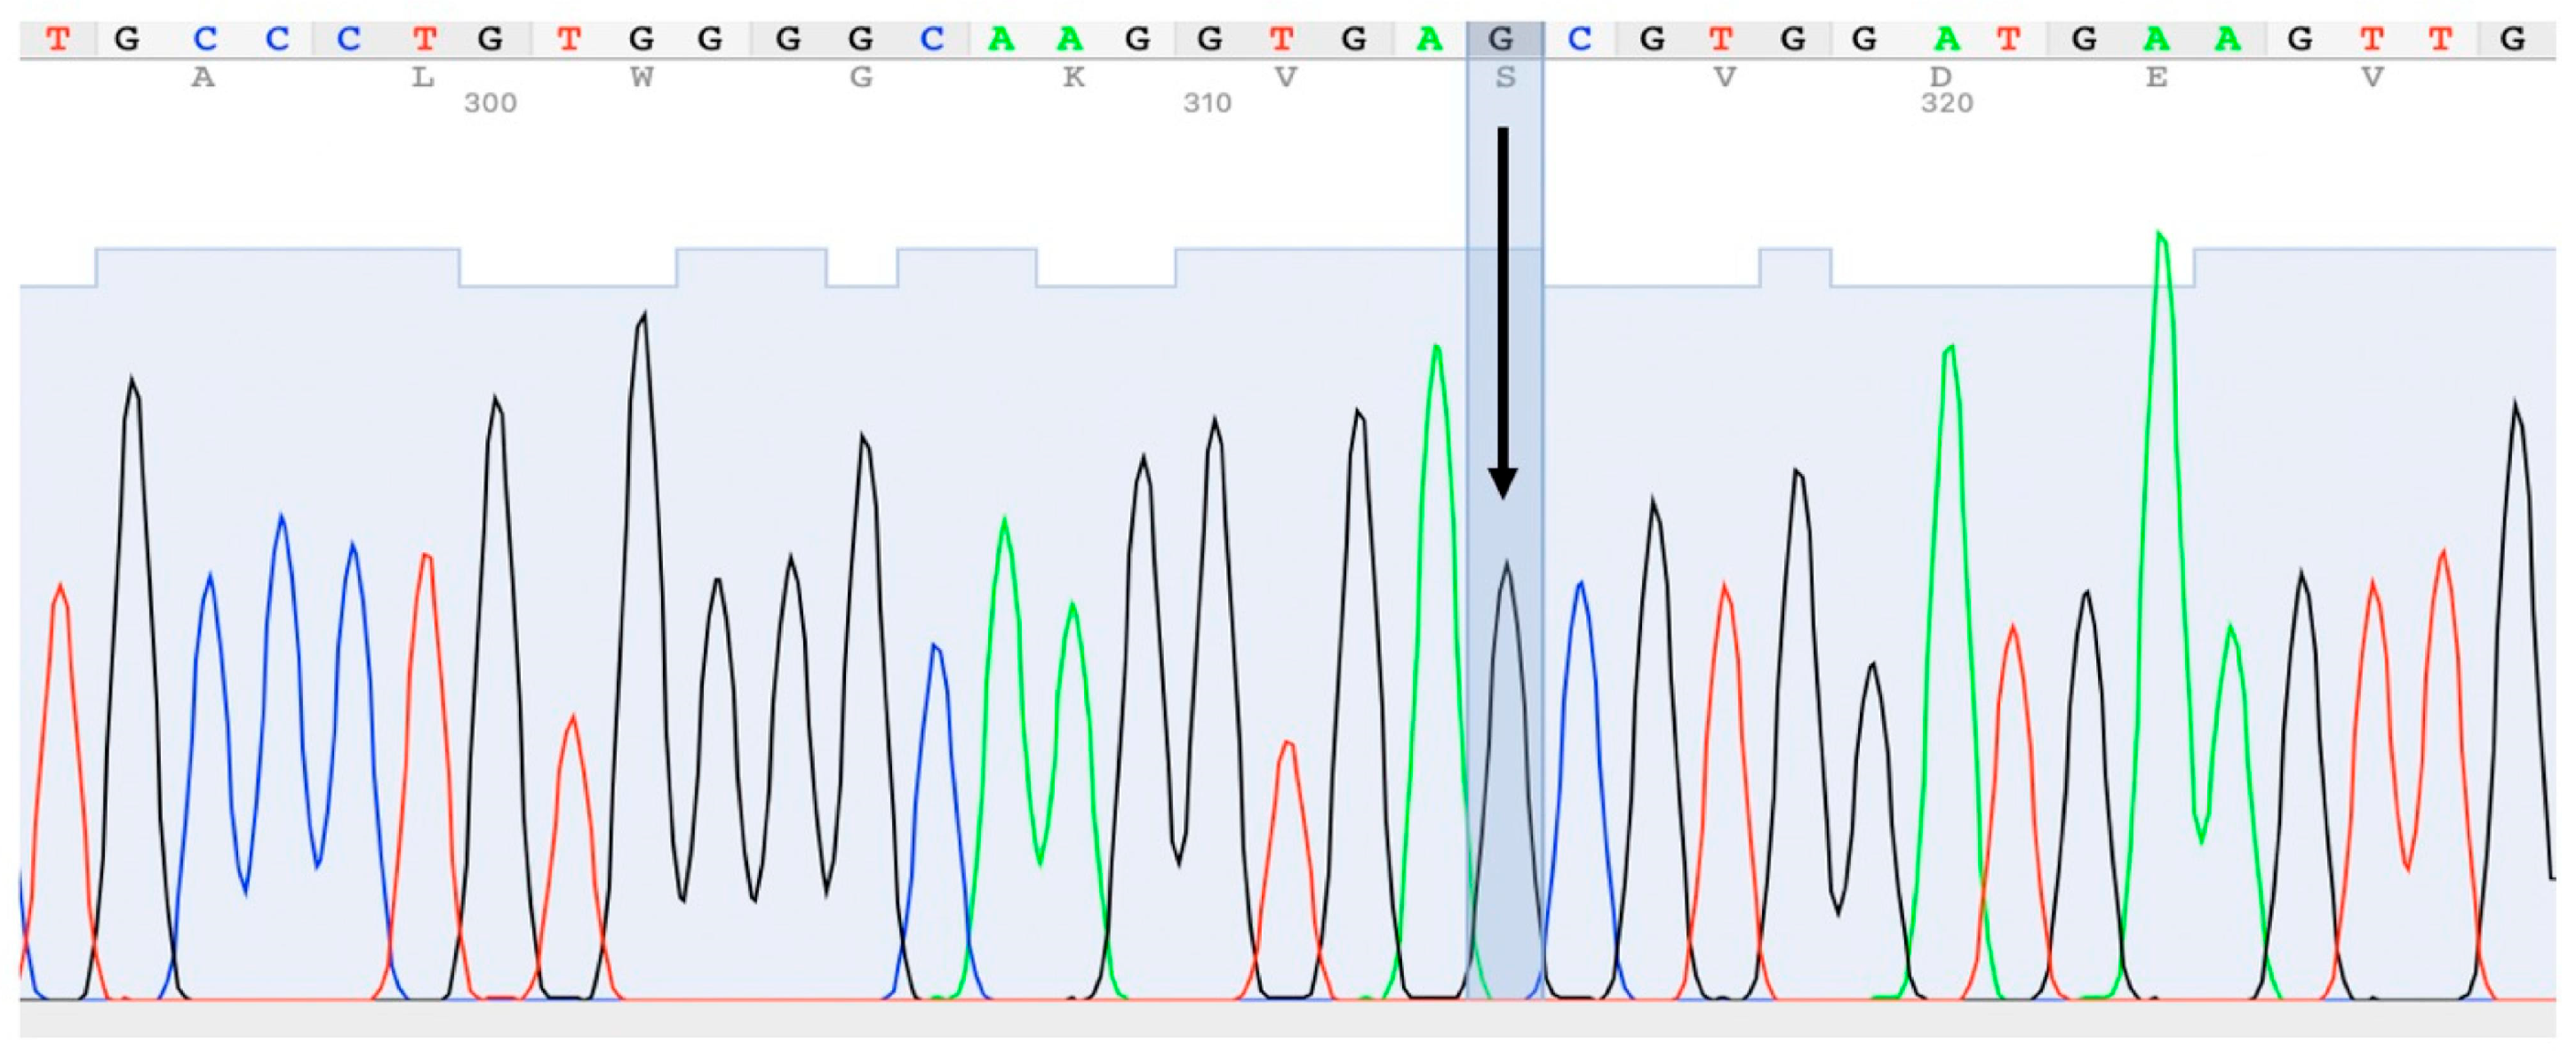
All GenoArray-positive samples for β-thal CD19 were confirmed by Sanger sequencing. Sequencing demonstrated a single base substitution (A→G) at codon 19, changing AAC to AGC (Figure 2). The individual homozygous for the Hb Malay variant (III-1, aged 15 years) showed a complete A→G substitution with no residual normal allele (Figure 3). No α-globin deletions covered by the THAL b8 SEA panel (−−SEA, −α3.7, −−FIL, −−SIRI, −−THAI, −HPFH-6, −−LEP, Del619) were detected. α-Globin deletions outside the scope of this assay panel were not assessed.
Figure 2.
Sanger sequencing chromatograms. (A) Normal β-globin showing the unaltered AAC codon at position 19. (B) Heterozygous β-thal CD19 showing both AAC and AGC at codon 19 (arrow indicates the mutation site). * refers to amino acid substitution caused by the nucleotide changes. Complete AAC→AGC substitution at codon 19 with only G peak (arrow) is observed and no re-sidual normal arrow, confirmed the homozigosity of the allele.
Figure 3.
Sanger sequencing result for subject III-1 (homozygous β-thal CD19). Complete AAC→AGC substitution at codon 19 with no residual normal allele (arrow), confirming homozygosity.
5. Discussion
This study reports one of the few documented examples of cascade molecular screening for the Hb Malay (HBB:c.59A>G) variant in a large Indonesian extended family, confirmed through dual molecular methods: GenoArray screening and Sanger sequencing.
Hb Malay is a β+-thalassemia-causing missense mutation in exon 1 of the β-globin gene at codon 19, specifically AAC→AGC (Asn→Ser) [7,9,10,11,13,15]. The molecular basis of this substitution has been well characterized: it reduces but does not abolish β-globin production, consistent with the β+ phenotype [24]. Heterozygous carriers typically present with mild microcytic anemia with low MCV and MCH, and slightly elevated HbA2 levels [8,12,25]. In the homozygous state or compound heterozygosity with other hemoglobinopathies, clinical severity increases, potentially resembling thalassemia intermedia or major, depending on the degree of β-globin chain imbalance [2,14,18,24,26,27]. Subject III-1, the sole individual homozygous for the Hb Malay variant (G/G, aged 15 years) identified in this family, could not be clinically evaluated within the scope of this study, as participants consented exclusively to molecular genetic screening. This represents a significant limitation of the present report. Complete hematological phenotyping of III-1—including hemoglobin level, MCV, MCH, HbA2, HbF, reticulocyte count, RDW, iron status, and clinical assessment—was not performed. Based on the published literature, homozygous Hb Malay has been reported to present as a mild thalassemia intermedia phenotype without transfusion dependence [14,24]; however, individual clinical expression may vary. Prospective clinical and hematological evaluation of this patient is strongly recommended as a priority for follow-up.
Regarding the proband’s hematological findings, the near-normal MCV of 80.5 fL warrants careful interpretation. Classic heterozygous β-thalassemia typically presents with distinctly reduced MCV (usually <80 fL) and elevated HbA2 (>3.5%). The proband’s MCV of 80.5 fL, while borderline, and the absence of HbA2 measurement make it impossible to confirm the thalassemia carrier phenotype on hematological grounds alone. Given the high prevalence of iron-deficiency anemia among Indonesian adolescent females, this condition cannot be excluded as a co-contributing factor to the observed mild anemia. The molecular finding of heterozygous Hb Malay confirms the proband’s genetic carrier status but does not establish the hematological phenotype of this specific individual. Pedigree analysis across three generations showed segregation consistent with autosomal recessive β-thalassemia inheritance, with 12 heterozygous carriers and one homozygous individual (III-1, aged 15).
The high proportion of variant-positive individuals identified in this study (13 of 16, 81.25%) is a direct consequence of the family-based cascade screening design, which by definition selects relatives of a carrier index case and enriches for the shared genetic variant. This finding should not be extrapolated to estimates of population-level carrier frequency of Hb Malay in Indonesia or in South Sumatran communities. The family’s origin from South Sumatra is clinically relevant: Hb Malay has been documented at a carrier frequency of approximately 5.3% in this population [18], a figure substantially lower than the ascertainment rate in our cohort. The Indonesian population is ethnically and genomically diverse, reflecting historical migration and inter-ethnic admixture across the archipelago. The inclusion of older relatives in generation I (ages 62–77 years) was intended to map the inheritance trajectory across three generations for genetic counseling purposes, not to provide epidemiological data. The family originated from South Sumatra, where Hb Malay has been documented at a carrier frequency of approximately 5.3% in the Malay ethnic population [18]. This highlights the importance of considering ethnic background when selecting mutation panels for molecular β-thal testing in Indonesia, where commonly screened mutations (IVS-1-5, HbE, CD41/42) may miss variants such as CD19 [16,17,28,29].
The absence of complete hematological data and HbA2 measurements for most family members is a recognized limitation. However, GenoArray and Sanger sequencing demonstrated full concordance, supporting the reliability of molecular-based cascade screening in resource-limited settings [30,31,32]. The primary contribution of this report lies not in the novelty of the Hb Malay mutation itself, but in demonstrating the inadequacy of conventional hematological triage for detecting this variant—as evidenced by the near-normal MCV in the proband and the failure of previous clinical workup to characterize the proband’s mother’s mutation. Molecular cascade screening enabled identification of 13 affected individuals across three generations, including a homozygous individual, in a family where standard screening criteria would likely have failed to prompt molecular investigation. While Hb Malay is well-documented in Malaysia [7,8,9,10,11,12,13] and Thailand [14,15,33], its documentation in Indonesia remains limited. This report contributes molecular epidemiological data and underscores the need to expand mutation screening panels to include rare variants such as CD19, particularly in populations of South Sumatran Malay ancestry. The clinical context of this case also highlights an important public health issue in Indonesia. The proband’s mother (II-4) had previously been informed of a thalassemia-associated anemia diagnosis at another facility, yet the specific mutation type was never disclosed to her. This lack of precise genetic information reflects the current state of thalassemia care in Indonesia, where hemoglobinopathy screening is not yet systematically integrated into routine healthcare, and awareness remains low compared to more commonly recognized conditions such as iron-deficiency anemia [4,6]. As a result, carriers and affected individuals may remain unaware of the hereditary implications for their offspring, delaying appropriate genetic counseling and cascade family screening. This case underscores the critical importance of not only detecting thalassemia but also ensuring that patients and families receive complete, accurate, and actionable genetic information following diagnosis.
6. Conclusions
The integration of GenoArray and Sanger sequencing provides a reliable approach for detecting rare β-globin gene variants in family-based settings. This report documents the Hb Malay (HBB:c.59A>G [NM_000518.5], p.Asn20Ser) variant in a three-generation Indonesian family among the largest pedigrees of this variant reported in Indonesia that was confirmed by dual molecular methods. The identification of multiple heterozygous carriers and one individual homozygous for the Hb Malay variant underscores the value of cascade molecular screening in settings where hemoglobin fractionation testing is limited. This report also highlights that conventional hematological triage may fail to identify Hb Malay carriers due to the near-normal MCV profile frequently observed in this variant. Complete hematological phenotyping of family members, particularly the homozygous individual, remains an important goal for future study. Population-based molecular epidemiological studies are needed to define the true prevalence of Hb Malay across Indonesia’s diverse ethnic landscape and to assess the cost-effectiveness of its inclusion in national thalassemia screening panels before broader prevention policy recommendations can be made.
Author Contributions
Conceptualization: C.A. and A.Z.; Methodology: C.A., G.P.S., M.F., Y.M., L.A.H., S. and A.L.; Formal analysis: C.A., R.P., S.P., P.S. and S.I.; Investigation: A.Z., G.P.S., M.F. and Y.M.; Data curation: C.A. and R.P.; Writing—original draft: C.A. and A.Z.; Writing—review and editing: C.A., S.P., P.S. and S.I.; Visualization: G.P.S. and M.F.; Supervision: C.A.; Project administration: C.A. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Ethics Committee of the Faculty of Medicine, Universitas Islam Negeri Syarif Hidayatullah Jakarta (protocol code B-019/F12/KEPK/TL.00/08/2025) on 8 August 2025.
Informed Consent Statement
Written informed consent was obtained from all participants (or their legal guardians) prior to inclusion in the study. Written informed consent for publication has been obtained from the participants.
Data Availability Statement
The data supporting the findings of this study are available from the corresponding author upon reasonable request, subject to institutional ethics approval.
Acknowledgments
The authors express sincere gratitude to the proband and all family members for their participation, and to the Faculty of Medicine and the Molecular Diagnostic and Research Center (MDRC) at UIN Syarif Hidayatullah Jakarta for institutional support. During the preparation of this manuscript, the authors used Claude (Anthropic) and Gemini (Google) for language editing and writing clarity. The authors have reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript: β-thal: β-thalassemia; CD19: codon 19 mutation; HBB: hemoglobin subunit beta gene; Hb Malay: hemoglobin Malay (HBB:c.59A>G); MCV: mean corpuscular volume; MCH: mean corpuscular hemoglobin; PCR: polymerase chain reaction.
References
- Langer, A.L. Beta-thalassemia. In GeneReviews®; Adam, M.P., Ed.; University of Washington: Seattle, WA, USA, 2000; Updated 2024. [Google Scholar]
- Bajwa, H.; Basit, H. Thalassemia. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2023. [Google Scholar]
- Sadiq, I.Z.; Abubakar, F.S.; Usman, H.S.; Abdullahi, A.D.; Ibrahim, B.; Kastayal, B.S.; Ibrahim, M.; Hassan, H.A. Thalassemia: Pathophysiology, diagnosis, and advances in treatment. Thalass. Rep. 2024, 14, 81–102. [Google Scholar] [CrossRef] [Scilit]
- Susanah, S.; Sari, N.M.; Prihatni, D.; Sinaga, P.O.; Trisaputra, J.O.; Rakhmilla, L.E.; Sribudiani, Y. Extended family thalassemia screening as a feasible alternative method to be implemented in identifying carriers in West Java, Indonesia. J. Community Genet. 2021, 13, 103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petrou, M. Genetic counselling. In Prevention of Thalassaemias and Other Haemoglobin Disorders, 2nd ed.; Old, J., Ed.; Thalassaemia International Federation: Nicosia, Cyprus, 2013. [Google Scholar]
- Wahidiyat, P.A.; Sari, T.T.; Rahmartani, L.D.; Iskandar, S.D.; Pratanata, A.M.; Yapiy, I.; Setianingsih, I.; Atmakusuma, T.D.; Lubis, A.M. Thalassemia in Indonesia. Hemoglobin 2022, 46, 39–44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, K.G.; Kutlar, F.; George, E.; Wilson, J.B.; Kutlar, A.; Stoming, T.A.; Gonzales-Redondo, J.M.; Huisman, T.H. Molecular characterization of beta-globin gene mutations in Malay patients with Hb E-beta-thalassaemia and thalassaemia major. Br. J. Haematol. 1989, 72, 73–80. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- George, E.; Huisman, T.H.; Yang, K.G.; Kutlar, F.; Wilson, J.B.; Kutlar, A.; Stoming, T.A.; Gonzales-Redondo, J.M.; Faridah, K.; Khalid, A.K. First observation of haemoglobin Malay alpha 2B2 26 (B1) Asn→Ser: A case report. Med. J. Malays. 1989, 44, 259–262. [Google Scholar]
- Rozitah, R.; Nizam, M.Z.; Nur Shafawati, A.R.; Nor Atifah, M.A.; Dewi, M.; Kannan, T.P.; Ariffin, N.; Norsarwany, M.; Setianingsih, I.; Harahap, A.; et al. Detection of beta-globin gene mutations among Kelantan Malay thalassaemia patients by PCR-RFLP. Singap. Med. J. 2008, 49, 1046–1049. [Google Scholar]
- Hassan, S.; Ahmad, R.; Zakaria, Z.; Zulkafli, Z.; Abdullah, W.Z. Detection of β-globin gene mutations among β-thalassemia carriers and patients in Malaysia: Application of multiplex ARMS-PCR. Malays. J. Med. Sci. 2013, 20, 13–20. [Google Scholar] [PubMed]
- Koh, D.X.R.; Raja Sabudin, R.Z.A.; Mohd Yusoff, M.; Hussin, N.H.; Ahmad, R.; Othman, A.; Ismail, E. Molecular characterisation of α- and β-thalassaemia among indigenous Senoi Orang Asli communities in Peninsular Malaysia. Ann. Hum. Genet. 2017, 81, 205–212. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hassan, S.; Zulkafli, Z.; Saleh, R.M.; Ahmad, R.; Abdullah, W.Z. Β-globin gene mutations among β-thalassemia and β-variant patients in a teaching hospital in Universiti Sains Malaysia, Kubang Kerian, Kelantan. GMJ 2022, 33, 215–219. [Google Scholar]
- Asri, A.S.; Samsuddin, M.H.; Jalil, N.; Mohamad Tahir, N.; Hashim, H.; Azma, R.Z.; Esa, E.; Albert, R.A.; Alauddin, H. Characterization of hemoglobin Malay phenotypes in tertiary hospitals. Hemoglobin 2024, 48, 153–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fucharoen, S.; Sanchaisuriya, K.; Fucharoen, G.; Surapot, S. Molecular characterization of thalassemia intermedia with homozygous Hb Malay and Hb Malay/HbE in Thai patients. Haematologica 2001, 86, 657–658. [Google Scholar] [PubMed]
- Theingi, M.; Ruengdit, C.; Punyamung, M.; Pornprasert, S. Case Report: Two cases of Hb Malay (HBB: C.59A>G) found in Northern Thailand. J. Assoc. Med. Sci. 2025, 59, 80–86. [Google Scholar]
- Rujito, L.; Maritska, Z.; Sofro, A.S. Β-thalassemia mutation flow in Indonesia: A migration perspective. Thalass. Rep. 2023, 13, 253–261. [Google Scholar] [CrossRef] [Scilit]
- Hernaningsih, Y.; Syafitri, Y.; Indrasari, Y.N.; Rahmawan, P.A.; Andarsini, M.R.; Lesmana, I.; Moses, E.J.; Abdul Rahim, N.A.; Yusoff, N.M. Analysis of common beta-thalassemia mutations in East Java, Indonesia. Front. Pediatr. 2022, 10, 925599. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sari, D.P.; Wahidiyat, P.A.; Setianingsih, I.; Timan, I.S.; Gatot, D.; Kekalih, A. Hematological parameters in individuals with beta thalassemia trait in South Sumatra, Indonesia. Anemia 2022, 2022, 3572986. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iqbal, R.; Sidrah; Akhtar, A. Family screening of thalassemic patients and effectiveness of education in providing knowledge about prevention of thalassemia. Pak. J. Med. Health Sci. 2023, 17, 253. [Google Scholar] [CrossRef] [Scilit]
- Kaur, G.; Chatterjee, T.; Ahuja, A.; Sen, A. Challenges in diagnosis of thalassemia syndromes. Med. J. Armed Forces India 2024, 88, 632–637. [Google Scholar] [CrossRef] [Scilit]
- Cao, A.; Galanello, R. Beta-thalassemia. Genet. Med. 2010, 12, 61–76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adhiyanto, C.; Hendarmin, L.; Puspitaningrum, R. Pengenalan Dasar Teknik Bio-Molekuler [Basic Introduction to Biomolecular Techniques]; Deepublish: Yogyakarta, Indonesia, 2020. [Google Scholar]
- Adhiyanto, C.; Yamashiro, Y.; Hattori, Y.; Nitta, T.; Hino, M.; Matar, M.; Takagi, F.; Kimoto, M. A new β0-thalassemia mutation (codon 102, AAC>ATCAC) in coexistence with a heterozygous P4.2 Nippon gene. Hemoglobin 2013, 37, 227–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thein, S.L. The molecular basis of β-thalassemia. Cold Spring Harb. Perspect. Med. 2013, 3, a011700. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hariharan, P.; Gorivale, M.; Sawant, P.; Dalvi, R.; Mehta, P.; Nadkarni, A. Significance of genetic modifiers of hemoglobinopathies leading towards precision medicine. Sci. Rep. 2021, 11, 20906. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iyevhobu, K.O.; Lucky, E.O.; Okobi, T.J.; Usoro, E.R.; Ivie, A.A.; Ken-Iyevhobu, B.; Omokpo, V.O. Overview of beta-thalassemia. In Thalassemia Syndromes-New Insights and Transfusion Modalities; IntechOpen: Rijeka, Croatia, 2023. [Google Scholar] [CrossRef] [Scilit]
- Sharifi, A.; Mahdieh, N. HBB mutations and HbA2 level: Escaping the carrier screening programs. Clin. Case Rep. 2021, 9, 973–977. [Google Scholar] [PubMed]
- Adhiyanto, C.; Susianti, Y.; Rahmawati, N.M.; Badriah, F.; Harriati, Z. Screening of β-globin gene mutations in adolescent schoolgirls in rural Malang and Sukabumi City, Java Province, Indonesia. In Proceedings of the 1st International Integrative Conference on Health, Life and Social Sciences (ICHLaS 2017), Tangerang, Indonesia, 11–12 November 2017; pp. 9–12. [Google Scholar]
- Batubara, N.R.; Adhiyanto, C.; Fahmida, U.; Freisleben, H.J. Hemoglobin E allele screening in adolescent girls at Kepanjen and Gondanglegi Districts, Malang Regency, East Java-Indonesia. Adv. Health Sci. Res. 2017, 10, 5–8. [Google Scholar]
- Huang, R.; Liu, Y.; Xu, J.; Lin, D.; Mao, A.; Yang, L.; Zhong, G.; Wang, H.; Xu, R.; Chen, Y.; et al. Back-to-back comparison of third-generation sequencing and next-generation sequencing in carrier screening of thalassemia. Arch. Pathol. Lab Med. 2024, 148, 797–804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, J.; Li, J.; Lai, Q.; Yu, Y. Combined use of gap-PCR and next-generation sequencing improves thalassaemia carrier screening among premarital adults in China. J. Clin. Pathol. 2020, 73, 488–492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russo, R.; Marra, R.; Rosato, B.E.; Iolascon, A.; Andolfo, I. Genetics and genomics approaches for diagnosis and research into hereditary anemias. Front. Physiol. 2020, 11, 613559. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boonyawat, B.; Monsereenusorn, C.; Traivaree, C. Molecular analysis of beta-globin gene mutations among Thai beta-thalassemia children: Results from a single center study. Appl. Clin. Genet. 2014, 7, 253–258. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.