


Abstract
Subungual tumors are rare and often misdiagnosed, leading to unnecessary procedures or delayed treatment; thus, accurate identification of benign neoplasms such as fibrolipoma is essential to guide appropriate management. We report a 59-year-old man who presented with a several-year history of a painless subungual mass of the right great toe with progressive nail thinning and onychodystrophy. Imaging demonstrated soft-tissue swelling without bone involvement. Surgical exploration revealed two well-demarcated, lobulated subungual and periungual masses that were completely excised. Histopathology showed mature adipocytes with fibrous septa, and fluorescence in situ hybridization confirmed HMGA2 translocation without MDM2 or CDK4 amplification, establishing the diagnosis of fibrolipoma. Complete excision resulted in satisfactory nail regrowth at 1-year follow-up with no recurrence. This case highlights the importance of including fibrolipoma in the differential diagnosis of subungual masses and supports the value of histopathological and molecular analysis in achieving precise diagnosis and optimal surgical outcomes.
1. Introduction
Fibrolipoma is classified by the World Health Organization as a rare histologic subtype of traditional lipomas composed of mature adipocytes with fibrous connective tissue [1]. Lipomas of the nail unit are exceedingly rare because the onychodermis is fibrovascular and lacks a subcutaneous adipose layer [2].
Since the initial report by Baran in 1984 [3], 14 cases of nail unit lipoma have been documented in the literature. As summarized in Table 1 [2,3,4,5,6,7,8,9,10,11,12], 9 of these cases occurred in the subungual region and 5 in the periungual region. The mean age of affected patients was 54.5 years, with an overall male predominance. Most lesions were painless, though some caused discomfort when wearing footwear or led to mild movement restriction. All reported cases presented with nail changes, including nail plate elevation, thinning, splitting, and dystrophy. No recurrence has been documented in previously reported nail unit lipomas for which follow-up information was available, although the duration of follow-up was variable and often not systematically reported. Recently, Hao et al. [13] reported an eight-case series of toe lipomas that included one fibrolipoma case, underscoring the clinical relevance of this entity for podiatric practice. Notably, the single fibrolipoma in that series, like the other lipomas in the series, presented as a subcutaneous mass without reported involvement of the nail unit. We searched PubMed, Embase, Web of Science and Google Scholar from database inception to April 2026 using combinations of the terms “subungual lipoma,” “periungual lipoma,” “nail unit lipoma,” “fibrolipoma,” and “lipoma of the toe.” We also manually screened the reference lists of the retrieved articles (summarized in Table 1). Only cases of histologically confirmed lipoma involving the subungual or periungual tissues of the nail unit were included. Kitagawa et al. [9] described a conventional lipoma of the finger pulp with bone erosion; although the lesion was centered in the pulp rather than the nail unit proper, it produced secondary nail plate changes.
Table 1.
Summary of subungual and periungual lipoma cases reported in the scientific literature.
On ultrasound, lipomas are typically well-circumscribed, relatively homogeneous, iso- or hyperechoic relative to subcutaneous fat, and associated with little or no internal vascularity [5]. For equivocal cases, MRI may provide additional diagnostic value because adipose tissue typically shows high signal on T1- and T2-weighted sequences with suppression on fat-saturated images [14]. Among benign lipomatous tumors, spindle cell lipoma (SCL) and pleomorphic lipoma (PL) warrant particular attention in the differential diagnosis, because both may show prominent fibrous and spindle-cell components and have, albeit exceptionally, been reported in the subungual region [10,11]. SCL and PL represent two poles of a single morphologic spectrum that typically arises in the subcutis of the posterior neck, upper back, and shoulders of middle-aged and older men [15,16]. Histologically, SCL is characterized by a variable admixture of mature adipocytes and bland, CD34-positive spindle cells embedded in thick, refractile “ropey” collagen bundles, whereas PL additionally contains floret-type multinucleated giant cells that may simulate liposarcoma [15,16,17]. At the molecular level, SCL/PL characteristically harbor monoallelic deletions of 13q14 encompassing RB1, often accompanied by 16q loss, and accordingly show loss of nuclear Rb expression by immunohistochemistry, whereas conventional lipoma and its fibrolipoma variant retain Rb expression and frequently harbor HMGA2 rearrangements [15,18,19].
Preoperative diagnosis of nail unit lipomas is challenging because they mimic other nail tumors, including glomus tumor, subungual exostosis, and squamous cell carcinoma [3]. Imaging and histopathologic examination with immunohistochemical and molecular studies are essential for definitive diagnosis. We describe a case of simultaneous subungual and periungual fibrolipomas in a 59-year-old man, with emphasis on clinical, radiographic, and pathologic findings relevant to the podiatric physician.
2. Detailed Case Description
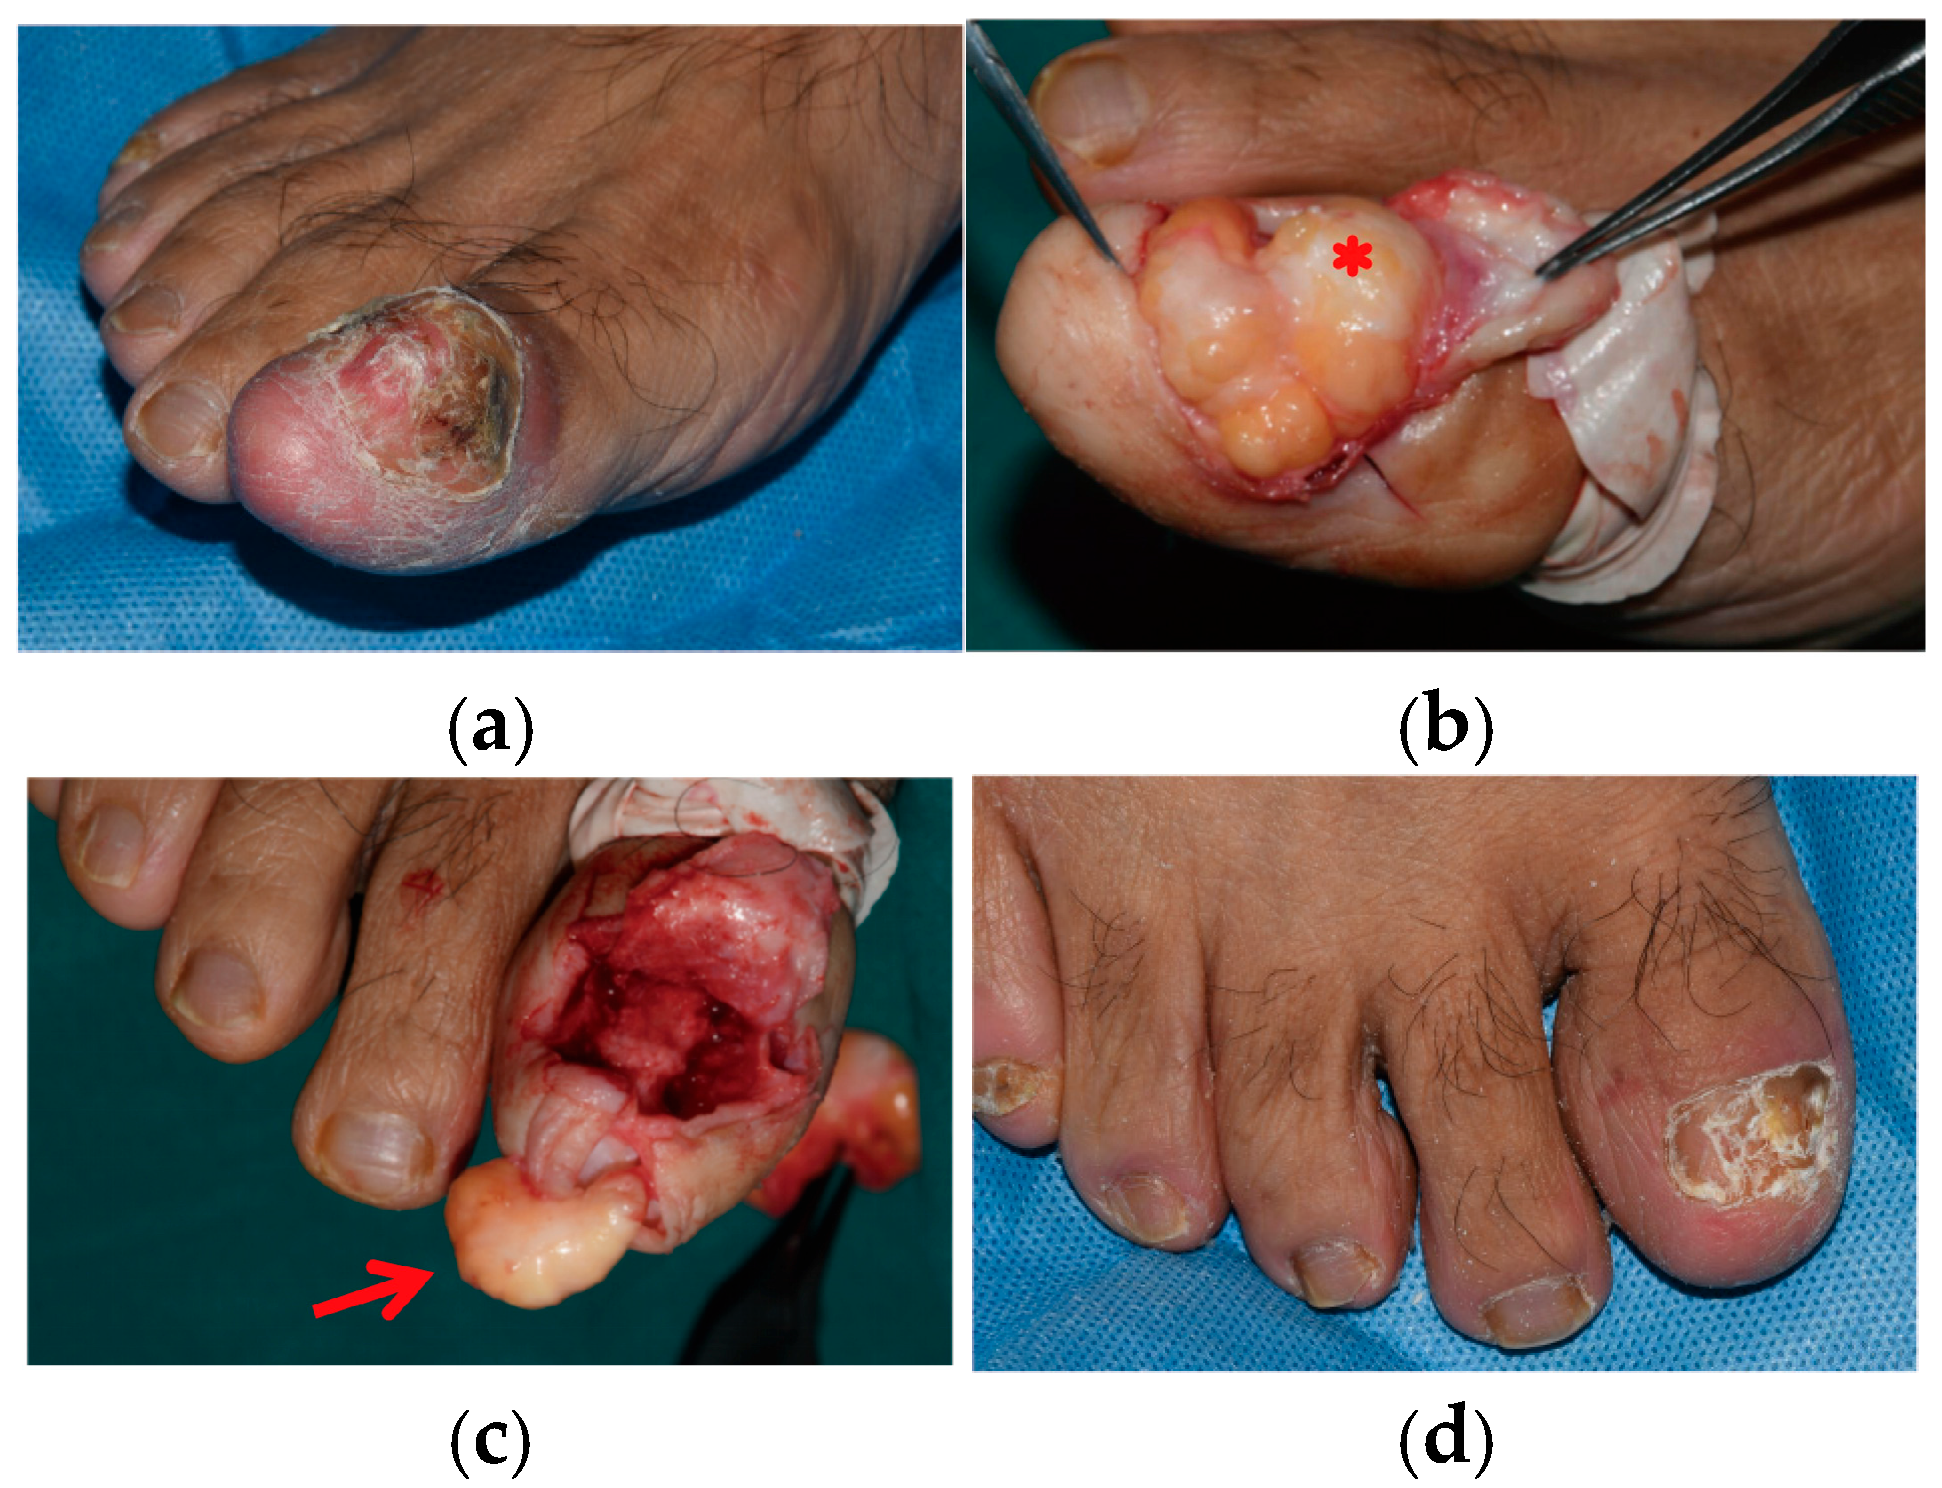
A 59-year-old man presented with a several-year history of a painless, nodular mass in the subungual and periungual regions of the right great toe. The affected nail plate showed marked thinning and onychodystrophy (Figure 1a). He reported no prior nail trauma or family history of similar conditions. Physical examination revealed swelling of the nail bed and distal phalanx with partial nail plate loss; the remaining nails were normal.
Radiography showed no phalangeal bone abnormality, although periarticular soft-tissue swelling was present without bone erosion. Ultrasound identified several nodules in the superficial soft tissue; the largest measured approximately 16 × 9 mm, with indistinct borders and irregular contour. Color Doppler imaging showed no significant internal vascularity. Surgical exploration revealed two well-demarcated, lobulated, yellowish, soft-tissue masses in the subungual and periungual areas; the lesions were not interconnected (Figure 1b,c). The larger subungual mass (approximately 16 × 10 mm) lay deep to the nail bed and encased the distal phalanx, while the smaller periungual mass (approximately 10 × 8 mm) was embedded in the lateral nail fold. Both specimens were excised and submitted separately for histopathologic examination, and each was independently confirmed as fibrolipoma.
Surgery was performed under digital block anesthesia. After partial avulsion of the thinned nail plate, a U-shaped incision was made in the nail bed and a longitudinal incision was made in the distal digit, and both masses were dissected free of the surrounding fibrovascular tissue with careful preservation of the nail matrix and germinal epithelium. The nail bed was repaired with 6-0 absorbable sutures, and the remaining nail plate was repositioned as a biologic dressing. Complete excision was assessed intraoperatively by gross inspection of the specimen capsules and was confirmed histologically by tumor-free margins in both specimens. The postoperative course was uneventful, without infection, hematoma, or secondary nail deformity.
Figure 1.
Clinical course from preoperative evaluation to 1-year postoperative follow-up. (a) Preoperative view of the right great toe showing marked nail thinning and onychodystrophy. (b,c) Intraoperative exposure after incising the nail bed and overlying skin; two well-demarcated, lobulated soft-tissue masses are evident (asterisk, subungual lesion; arrow, periungual lesion). (d) One year after complete excision, the nail plate has regrown and covers most of the nail bed without tumor recurrence.
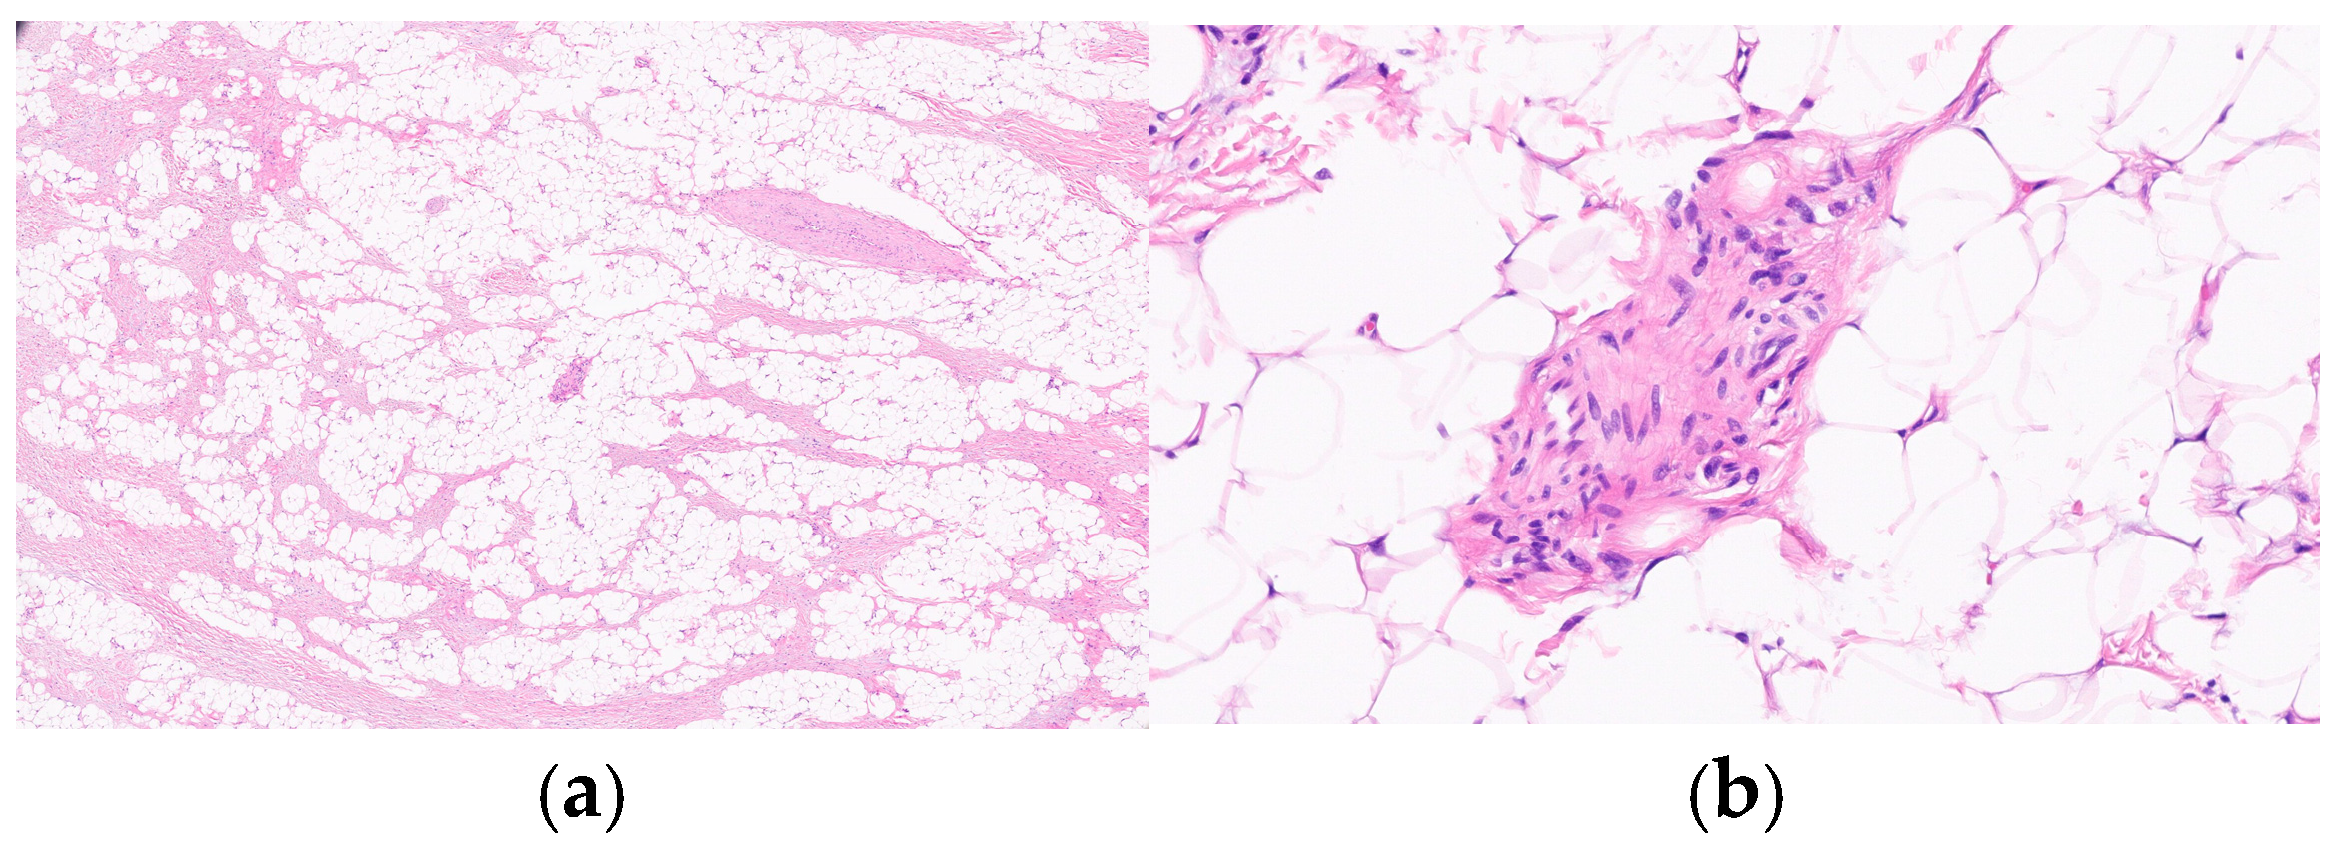
Histologic examination showed mature adipocytes admixed with fibrous bundles and scattered plump spindle cells. These spindle cells were sparse, cytologically bland stromal cells confined to the fibrous septa, with no ropey collagen bundles or floret-type multinucleated giant cells (Figure 2); partial S-100 positivity, focal p53 positivity, and a Ki-67 proliferative index of 2%; CD34, desmin, SMA, MDM2, and CDK4 were negative. Fluorescence in situ hybridization, performed on the larger subungual specimen, confirmed HMGA2 gene translocation without CDK4 or MDM2 amplification, establishing the diagnosis of fibrolipoma in concordance with the identical morphology of the periungual specimen.
Figure 2.
Histopathologic appearance of the excised specimen. (a) Mature adipocytes are interspersed with variably prominent fibrous septa containing scattered bland spindle cells (H&E, original magnification ×40). (b) Higher-magnification view of the fibrous septa (H&E, original magnification ×200).
At 1-year follow-up after complete surgical excision, the surgical site had healed well with satisfactory nail plate regrowth from the proximal nail fold (Figure 1d). No recurrence was observed, and both function and cosmesis of the right toe were excellent.
3. Discussion
To our knowledge, this is the first report of simultaneous, separate subungual and periungual fibrolipomas within the same digit, presenting as a painless subungual mass with progressive nail thinning and onychodystrophy. In our patient, fluorescence in situ hybridization confirmed an HMGA2 translocation without CDK4 or MDM2 amplification. This result verifies the clonal chromosomal abnormality that is characteristic of benign lipomatous tumors [18], and helps rule out atypical lipomatous tumor and well-differentiated liposarcoma [14,20].
In our patient, plain radiography was useful mainly to exclude an underlying osseous lesion such as subungual exostosis [10]; it showed periarticular soft-tissue swelling without bone erosion but could not further characterize the soft-tissue abnormality. High-frequency ultrasound revealed multiple superficial nodules within the nail unit, the largest of which measured approximately 16 × 9 mm, with indistinct margins, irregular contour, and no significant internal vascularity on color Doppler. These findings were not the classic sonographic pattern most commonly reported for subcutaneous lipomas [5]. Rather than confirming the diagnosis, ultrasound in this setting was nonspecific and may overestimate the number of nodules or fail to define whether adjacent echogenic foci represent separate lesions or lobulated components of the same tumor, particularly within the complex anatomy of the nail unit. Therefore, the definitive number, location, and nature of the lesions were established by operative exploration and separate histopathologic confirmation of two discrete, non-interconnected masses. Given the atypical sonographic features in the present case, histopathologic examination with ancillary studies remained essential for diagnosis.
Definitive diagnosis in our case was established via histopathologic examination. The excised specimens contained well-differentiated mature adipocytes partitioned by fibrous septa into a lobular architecture, with no myxoid stroma or lipoblasts. The sparse plump spindle cells within the fibrous septa were interpreted as bland stromal fibroblasts rather than a true spindle-cell neoplastic component: they were CD34 negative, lacked the ropey collagen bundles characteristic of spindle cell lipoma, and no floret-type multinucleated giant cells suggestive of pleomorphic lipoma were identified [15]. The predominance of mature adipocytes partitioned by dense fibrous septa, in combination with the HMGA2 rearrangement and the absence of MDM2 or CDK4 amplification, supports the diagnosis of fibrolipoma over spindle cell lipoma, pleomorphic lipoma, angiomyxolipoma, and atypical lipomatous tumor. Immunohistochemistry showed partial S-100 positivity, while CD34, desmin, SMA, MDM2, and CDK4 all tested negative, an immunoprofile typical of fibrolipoma [14]. Combined with the molecular findings, these results allowed exclusion of the main differential diagnoses for a subungual mass, including glomus tumor, subungual exostosis, epidermoid cyst, and squamous cell carcinoma [11].
In the present case, the absence of ropey collagen bundles and floret-type giant cells, the CD34 negativity of the sparse stromal spindle cells confined to the fibrous septa, and the demonstration of an HMGA2 translocation collectively favor fibrolipoma over SCL/PL. Where morphologic overlap persists, Rb immunostaining—retained in fibrolipoma but lost in SCL/PL—may serve as a useful adjunctive discriminator [19].
Complete surgical excision, confirmed by tumor-free histologic margins in both specimens, achieved an excellent outcome for our patient. Preservation of the nail matrix and germinal epithelium facilitated postoperative nail regrowth, with satisfactory nail bed coverage and excellent function and cosmesis at the 1-year follow-up. Our patient remained recurrence-free at 1 year; nevertheless, given the limited follow-up data in the literature, longer-term surveillance is advisable before definitive prognostic conclusions can be drawn.
4. Conclusions
Subungual and periungual fibrolipomas are rare benign tumors that warrant inclusion in the differential diagnosis of painless subungual nodules with nail dystrophy. Accurate diagnosis requires clinical correlation, imaging, and histopathologic examination with immunohistochemical and molecular studies. Complete surgical excision with preservation of the nail matrix offers excellent functional and cosmetic outcomes.
Author Contributions
X.T.: Writing—original draft, data curation, and methodology. Z.Z.: Writing—original draft, data curation, and investigation. T.W.: Supervision, writing—review and editing. H.L.: Supervision and writing—review and editing. S.X.: Supervision, writing—review and editing, validation. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This case report was prepared in accordance with the Declaration of Helsinki. The Ethics Committee of West China Hospital, Sichuan University reviewed the protocol and determined that formal ethical approval was not required for this retrospective case report.
Informed Consent Statement
Written informed consent for publication of this case report and accompanying images was obtained from the patient.
Data Availability Statement
The datasets presented in this study are not publicly available due to patient privacy concerns but are available from the corresponding author upon reasonable request.
Acknowledgments
The authors affirm that no generative artificial intelligence tools were utilized at any stage of this work, including the research design, data collection and analysis, manuscript preparation, or image editing.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| CD34 | Cluster of Differentiation 34 |
| CDK4 | Cyclin-Dependent Kinase 4 |
| HMGA2 | High-Mobility Group AT-Hook 2 |
| MDM2 | Mouse Double Minute 2 homolog |
| PL | Pleomorphic lipoma |
| SCL | Spindle cell lipoma |
| SMA | Smooth Muscle Actin |
References
- Tandon, A.; Srivastava, A.; Jaiswal, R.; Gaur, A. Oral fibrolipoma: A rare clinicopathological entity. J. Oral Maxillofac. Pathol. 2023, 27, 537–539. [Google Scholar] [CrossRef] [Scilit]
- Velez, N.F.; Telang, G.H.; Robinson-Bostom, L.; Jellinek, N.J. Subungual lipoma: Presenting as longitudinal nail splitting. Dermatol. Surg. 2014, 40, 1435–1437. [Google Scholar] [CrossRef] [Scilit]
- Baran, R. Periungual lipoma at an unusual site. J. Dermatol. Surg. Oncol. 1984, 10, 32–33. [Google Scholar] [CrossRef] [Scilit]
- Richert, B.; Andre, J.; Choffray, A.; Rahier, S.; de la Brassinne, M. Periungual lipoma: About three cases. J. Am. Acad. Dermatol. 2004, 51, S91–S93. [Google Scholar] [CrossRef] [Scilit]
- Gallouj, S.; Aqil, N.; Zahra Mernissi, F. Periungual lipoma: An unusual site. Ann. Dermatol. Venereol. 2019, 146, 121–124. [Google Scholar] [CrossRef] [Scilit]
- Failla, J.M. Subungual lipoma, squamous carcinoma of the nail bed, and secondary chronic infection. J. Hand Surg. 1996, 21, 512–514. [Google Scholar] [CrossRef] [Scilit]
- Bardazzi, F.; Savoia, F.; Fanti, P.A. Subungual lipoma. Br. J. Dermatol. 2003, 149, 418. [Google Scholar] [CrossRef] [Scilit]
- Sanchez Sambucety, P.; Alonso Alonso, T.; Gil Agapito, P.; Gonzalez Moran, A.; Rodriguez Prieto, M.A. Subungual angiomyxolipoma. Dermatol. Surg. 2007, 33, 508–509. [Google Scholar] [CrossRef] [Scilit]
- Kitagawa, Y.; Tamai, K.; Kim, Y.; Hayashi, M.; Makino, A.; Takai, S. Lipoma of the finger with bone erosion. J. Nippon Med. Sch. 2012, 79, 307–311. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Kwon, N.H.; Kim, H.S.; Kang, H.; Lee, J.Y.; Kim, H.O.; Kang, S.J.; Park, Y.M. Subungual spindle cell lipoma. Int. J. Dermatol. 2013, 52, 636–638. [Google Scholar] [CrossRef] [Scilit]
- Nakamura, R.; Valgas, N.; Bolzani, F.; Bonatto, D.; Kac, B.; de Brito, F. Subungual spindle cell lipoma: Case report: P6700. J. Am. Acad. Dermatol. 2013, 68, AB109. [Google Scholar] [CrossRef] [Scilit]
- Cunha, N.; Sousa, V.C.; Pinheiro, R.; Lencastre, A. And next… adnexa: Subungual lipoma. Eur. J. Dermatol. 2017, 27, 448–449. [Google Scholar] [CrossRef] [Scilit]
- Hao, X.; Mirkin, G.; Freedman, D.J.; Beiser, I.; Firestone, L.; Grant, D. Lipomas of the toes: An eight-case series. J. Am. Podiatr. Med. Assoc. 2023, 113, 20285. [Google Scholar] [CrossRef] [Scilit]
- Nishio, J.; Ideta, S.; Aoki, M.; Hamasaki, M.; Nabeshima, K.; Iwasaki, H.; Naito, M. Fibrolipoma of the ring finger: MR imaging and histological correlation. In Vivo 2013, 27, 541–544. [Google Scholar]
- Ohshima, Y.; Nishio, J.; Nakayama, S.; Koga, K.; Aoki, M.; Yamamoto, T. Spindle cell lipoma and pleomorphic lipoma: An update and review. Cancer Diagn. Progn. 2023, 3, 282–290. [Google Scholar] [CrossRef] [Scilit]
- Enzinger, F.M.; Harvey, D.A. Spindle cell lipoma. Cancer 1975, 36, 1852–1859. [Google Scholar] [CrossRef] [Scilit]
- Shmookler, B.M.; Enzinger, F.M. Pleomorphic lipoma: A benign tumor simulating liposarcoma. A clinicopathologic analysis of 48 cases. Cancer 1981, 47, 126–133. [Google Scholar] [CrossRef] [Scilit]
- Panagopoulos, I.; Gorunova, L.; Bjerkehagen, B.; Lobmaier, I.; Heim, S. The recurrent chromosomal translocation t(12;18)(q14~15;q12~21) causes the fusion gene HMGA2-SETBP1 and HMGA2 expression in lipoma and osteochondrolipoma. Int. J. Oncol. 2015, 47, 884–890. [Google Scholar] [CrossRef] [Scilit]
- Chen, B.J.; Mariño-Enríquez, A.; Fletcher, C.D.; Hornick, J.L. Loss of retinoblastoma protein expression in spindle cell/pleomorphic lipomas and cytogenetically related tumors: An immunohistochemical study with diagnostic implications. Am. J. Surg. Pathol. 2012, 36, 1119–1128. [Google Scholar] [CrossRef] [Scilit]
- Thway, K.; Flora, R.; Shah, C.; Olmos, D.; Fisher, C. Diagnostic utility of p16, CDK4, and MDM2 as an immunohistochemical panel in distinguishing well-differentiated and dedifferentiated liposarcomas from other adipocytic tumors. Am. J. Surg. Pathol. 2012, 36, 462–469. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the American Podiatric Medical Association. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.