


Case report
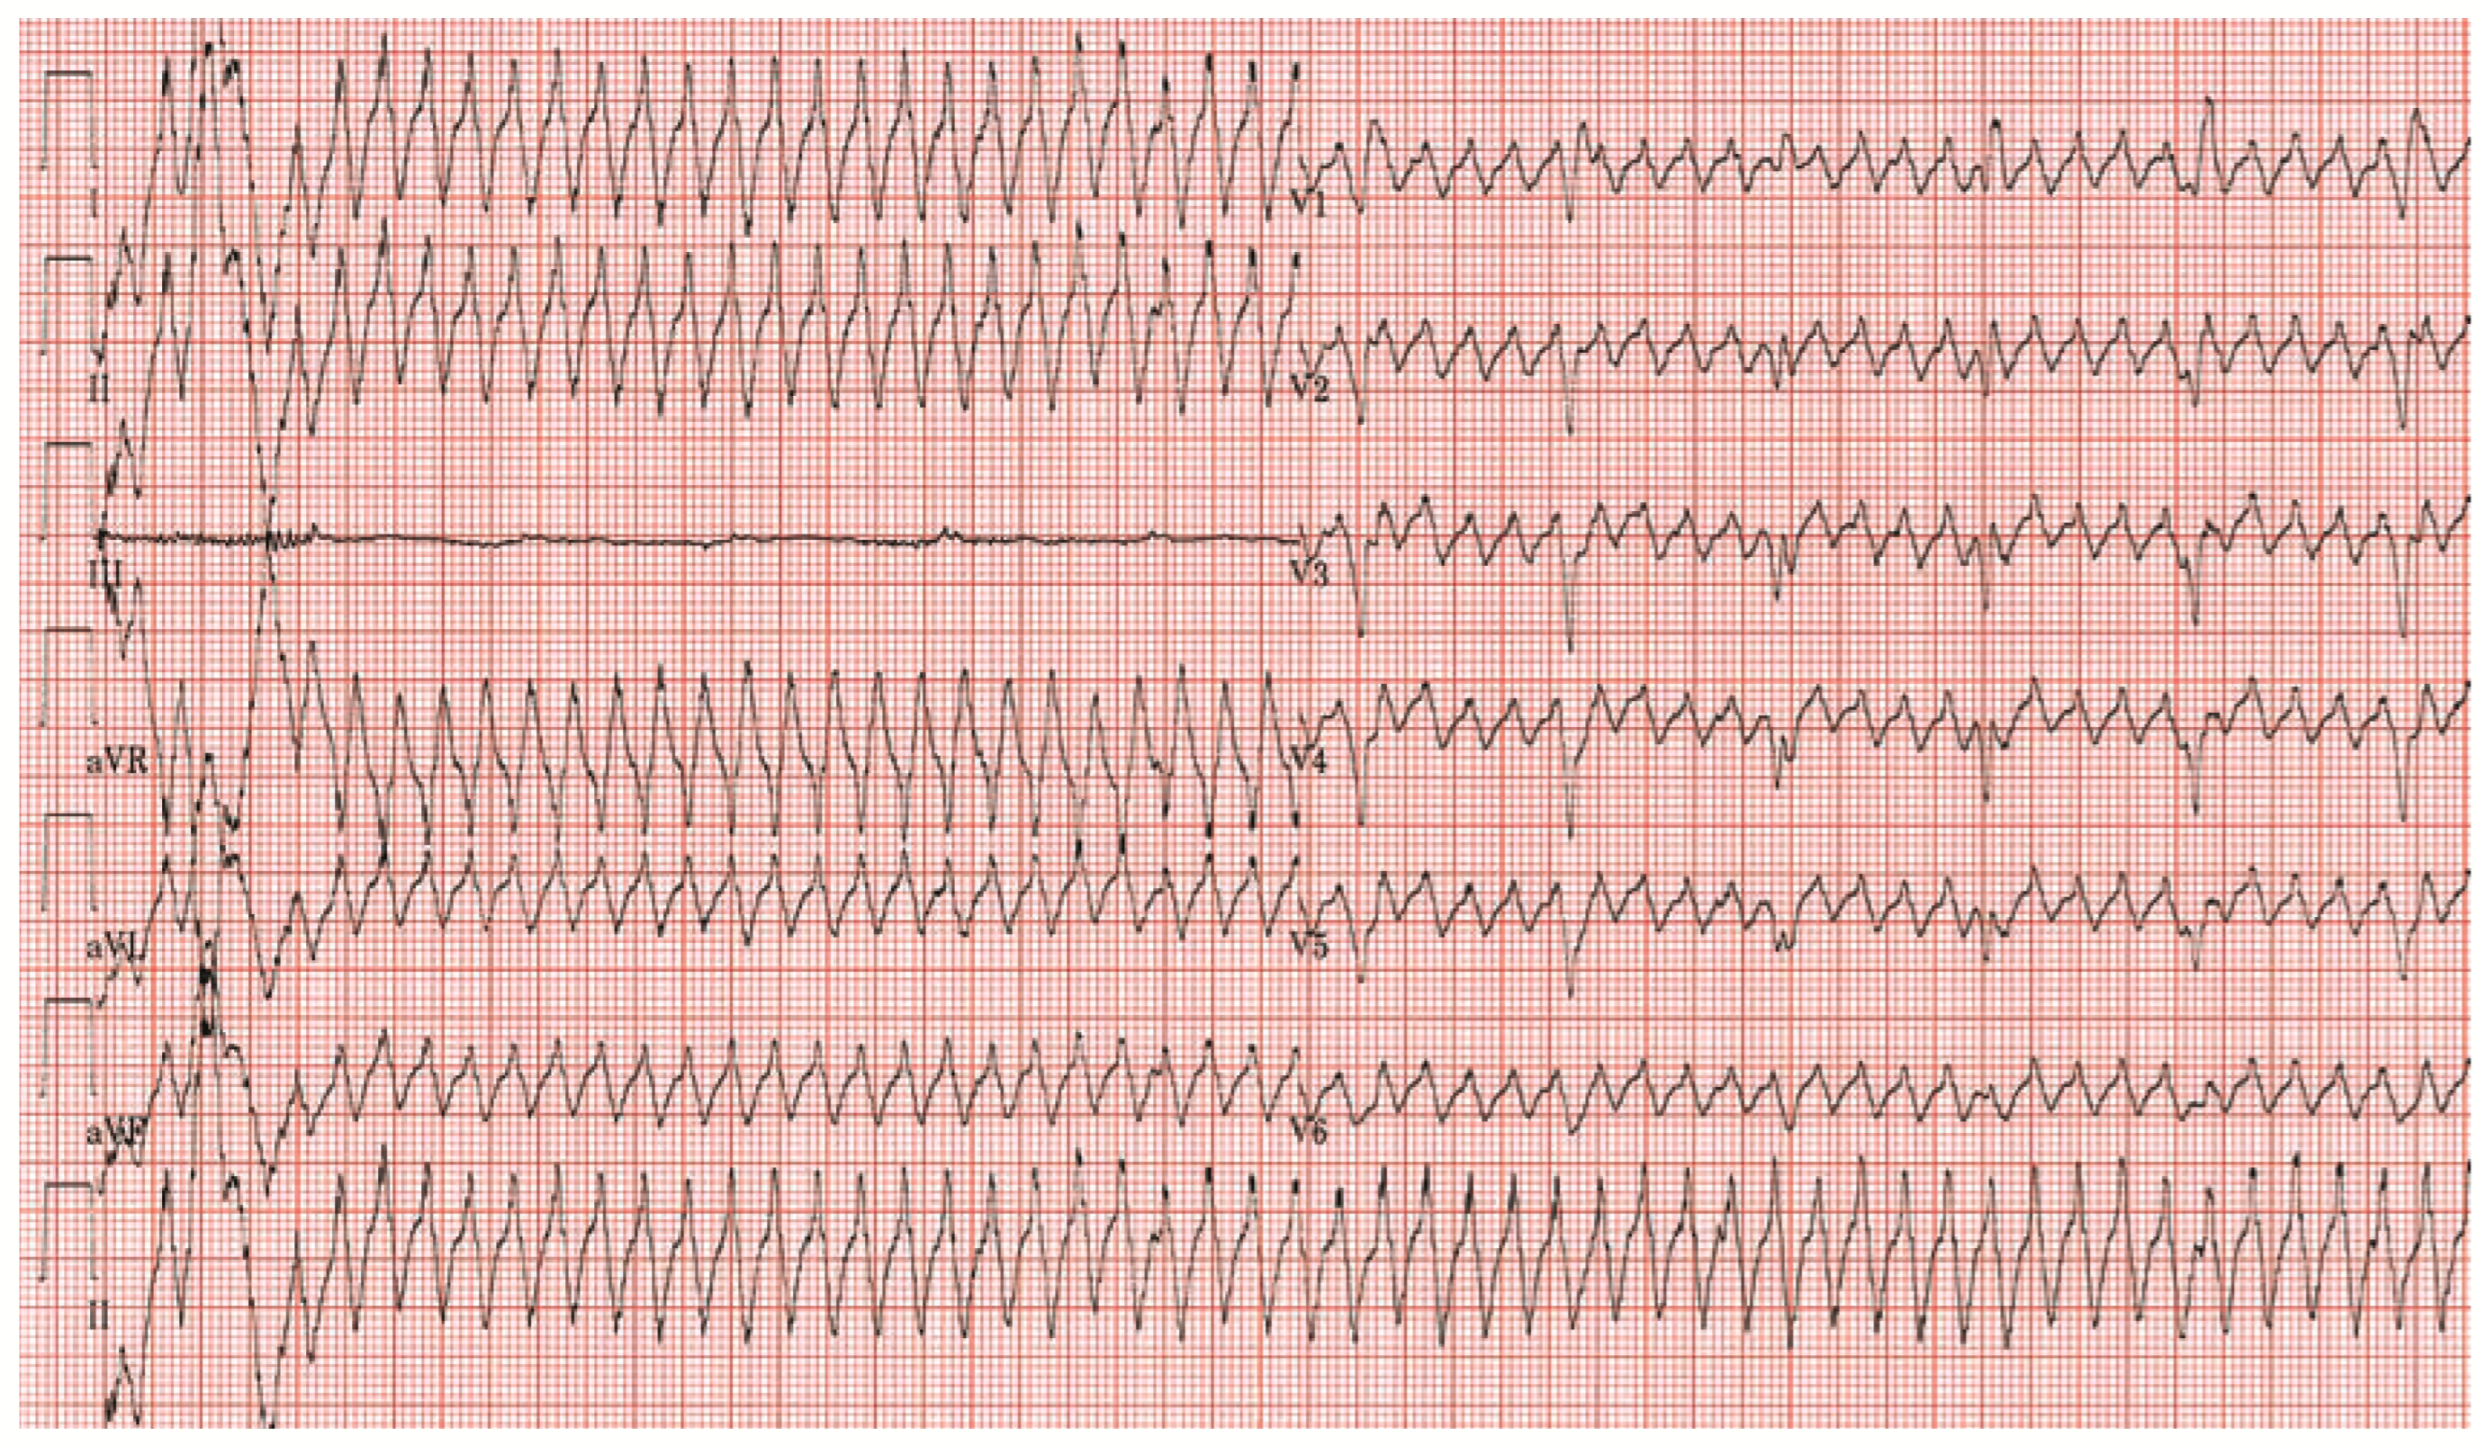
A 72-year-old man was admitted because of cardiogenic shock due to acute anterior myocardial infarction with ST-segment elevation. Percutaneous coronary intervention was performed with stenting of the occluded proximal left anterior descending artery with two sirolimus-eluting stents and placement of intra-aortic balloon pump. Mechanical ventilation and haemodynamic support with dobutamine and norepinephrine were required. Later on, anti-arrhythmic therapy with amiodarone was needed because of atrial fibrillation. Only after electrical cardioversion sinus rhythm was reestablished. In sustained low output heart failure dobutamine was replaced by levosimendan (Simdax®). Furthermore, renal replacement therapy was started because of progressive renal failure. During continuous venovenous haemofiltration (Cobe Prisma system®), Gambro Healthcare, USA) the patient developed an apparent atrial flutter with variable atrioventricular conduction (fig. 1). Is this the correct diagnosis?
Explanatory answers
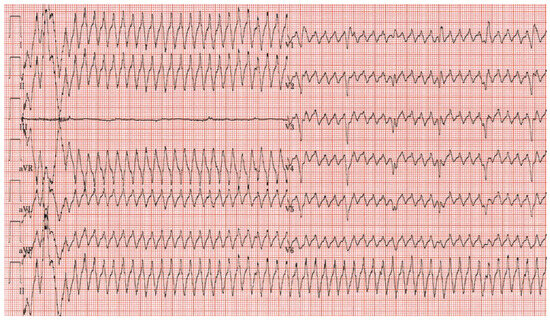
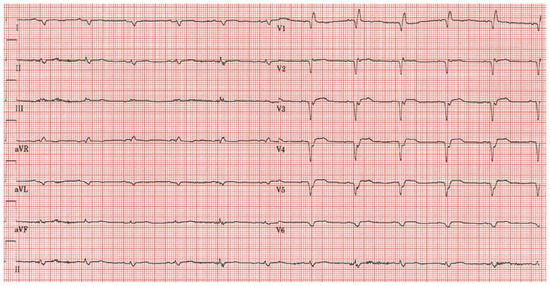
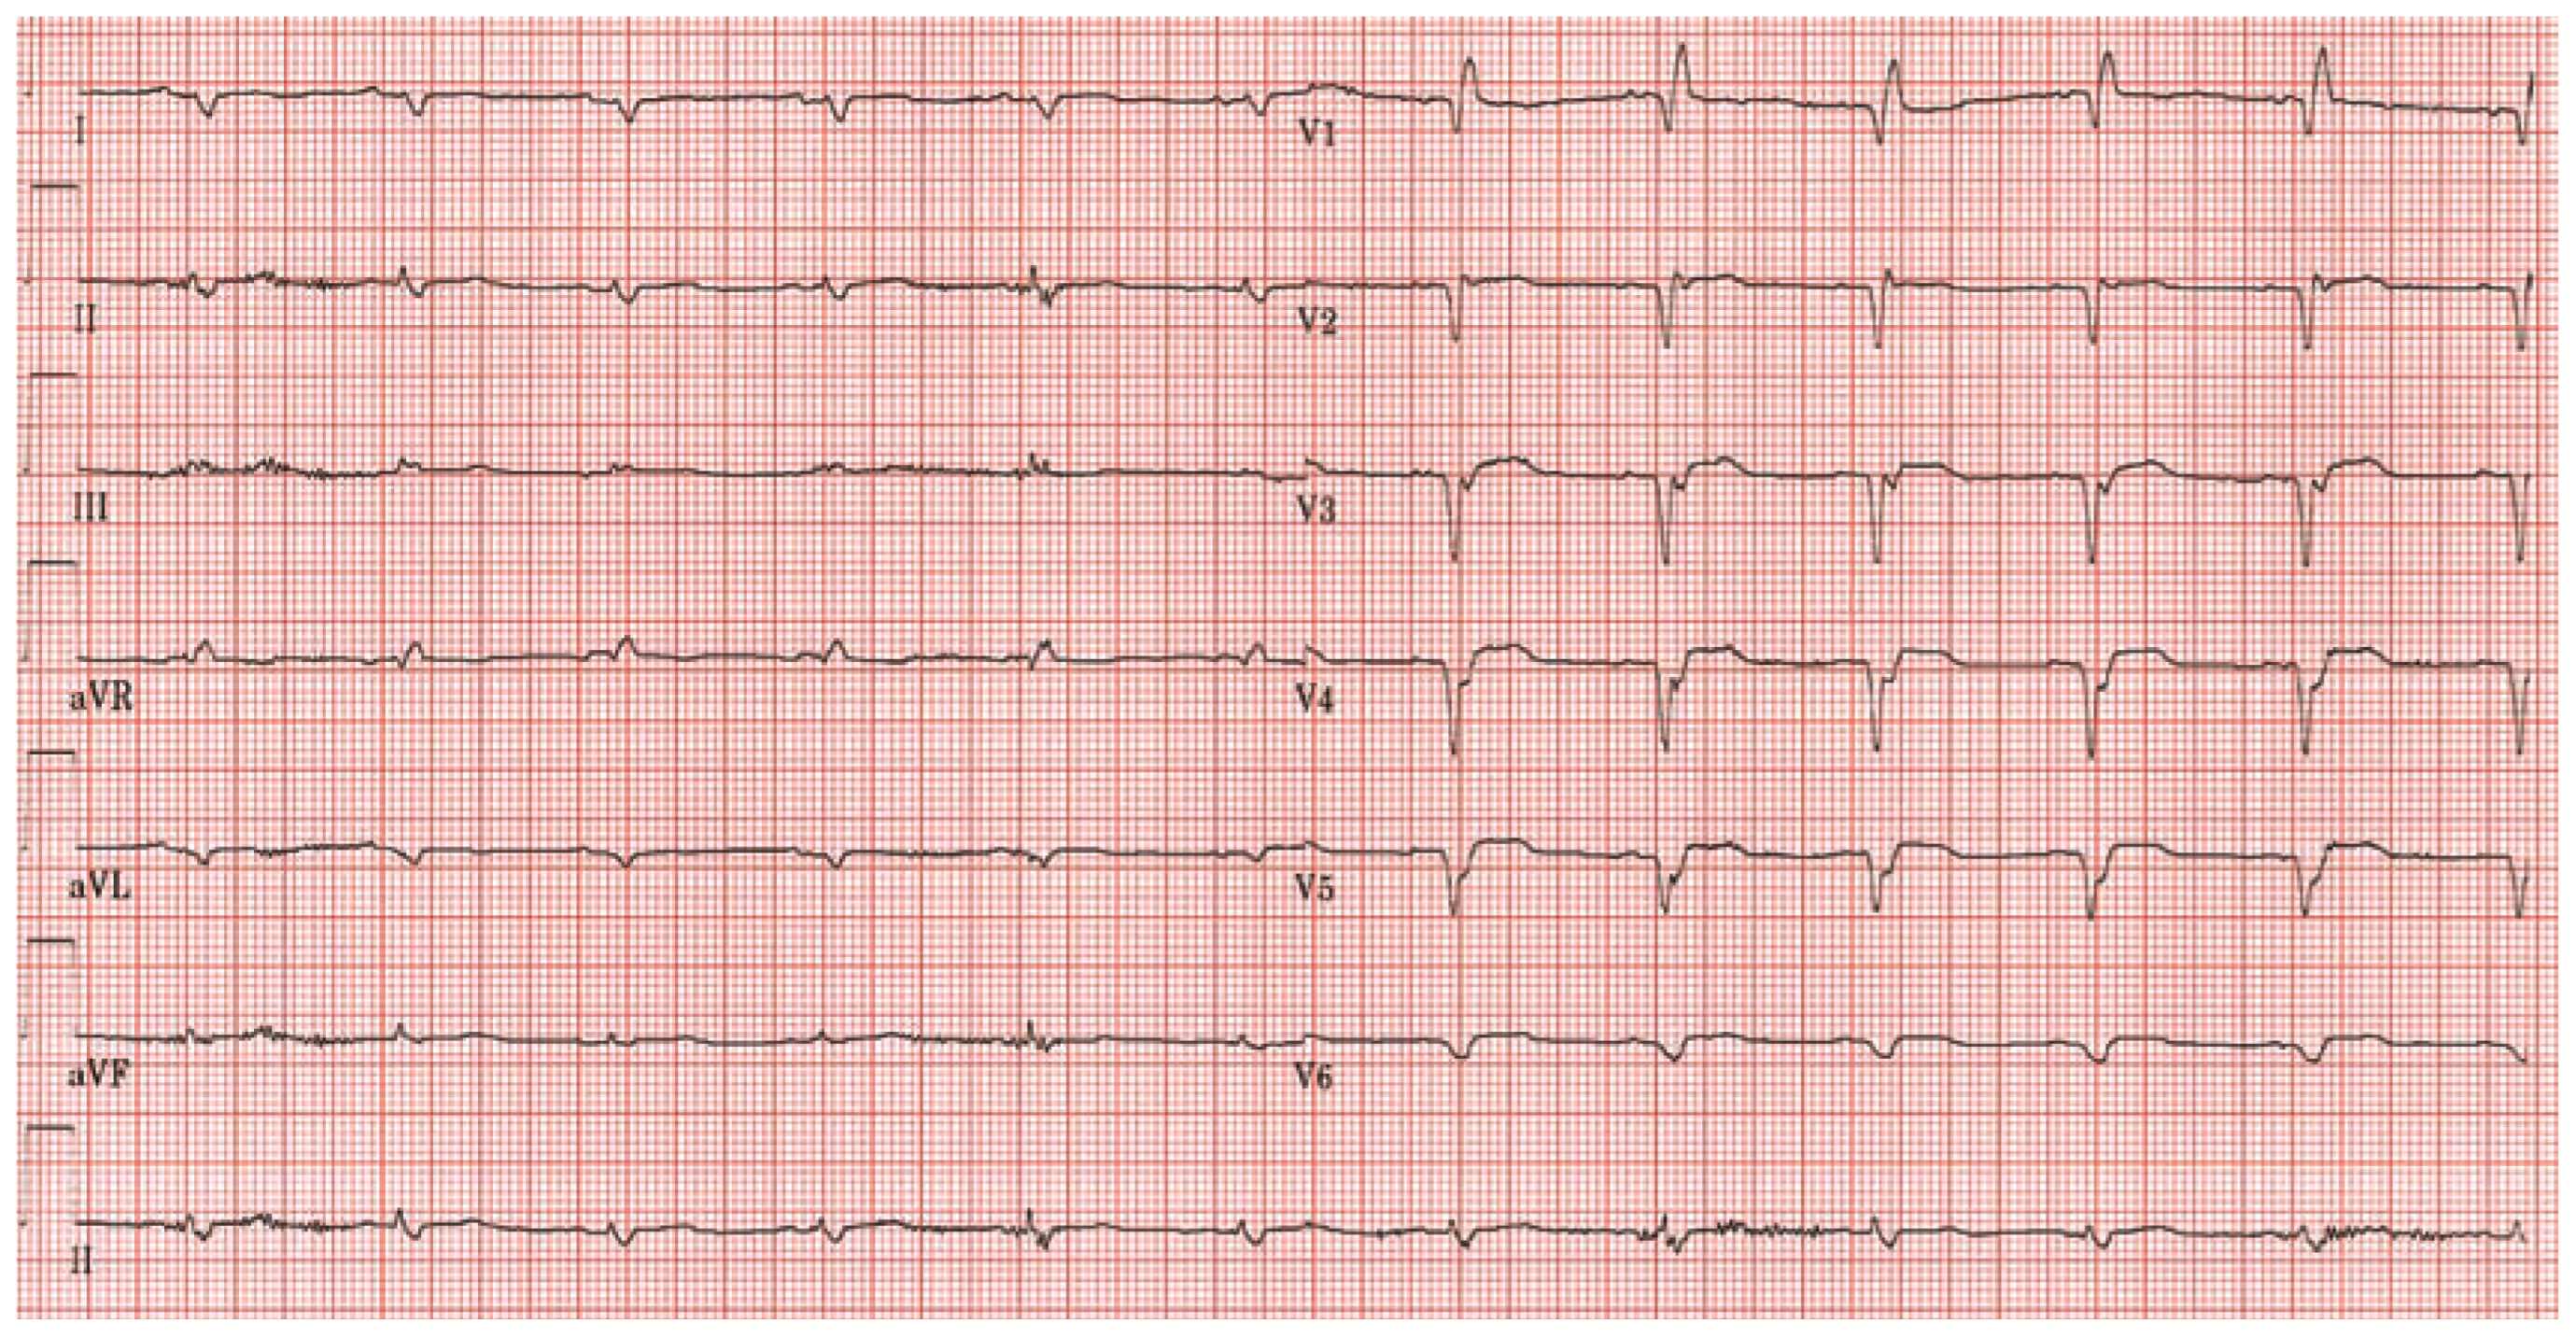
Shortly after initiation of haemofiltration the electrocardiogram (ECG) showed an atrial arrhythmia with saw-toothed flutter waves consistent with atrial flutter (Figure 1). Immediately after turning off the haemofiltration system, normal sinus rhythm was recorded on ECG (Figure 2). Therefore, diagnosis of artifactual atrial flutter was confirmed. Clinical course was further complicated and the patient eventually died 42 days after admission.
Figure 1.
Standard 12-lead ECG during continuous venovenous haemofiltration showing flutter waves in all precordial leads (sweep speed of 25 mm per second).
Figure 2.
Standard 12-lead ECG at time haemofiltration was turned off (sweep speed of 25 mm per second).
Atrial arrhythmias frequently occur in critically ill patients in need of intravenous inotropic support. During the course of continuous venovenous haemofiltration, artifactual flutter waves can be induced by electrical interference caused by static electricity which is generated by the rotational movement of the blood pumps [1]. Tremor-induced ECG artifacts can also impress as pseudoatrial flutter [2].
In conclusion, physicians should be aware of electrocardiographic artifacts. Several causes have been described [3,4]. Misdiagnosis can lead to unnecessary diagnostic or therapeutic interventions such as administration of antiarrhythmics, oral anticoagulation, diagnostic cardiac catheterisation, and even placement of an implantable cardioverter defibrillator [5].
References
- Graansma, C.; Liu, T.T.; Tobe, S.W. A simple solution to pseudoarrhythmia during continuous renal replacement therapy. CANNT J 2004, 14, 24–5. [Google Scholar] [PubMed]
- Vanerio, G. Tremor as a cause of pseudoatrial flutter. Am. J. Geriatr. Cardiol. 2007, 16, 106–8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhatia, L.; Turner, D.R. Parkinson’s tremor mimicking ventricular tachycardia. Age Ageing 2005, 34, 410–1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Austin, S.M.; Flach, S.D.; Gaines, C.M. Atrial flutter simulated by a portable compact disk player. Mayo. Clin. Proc. 2007, 82, 383–4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knight, B.P.; Pelosi, F.; Michaud, G.F.; Strickberger, S.A.; Morady, F. Clinical consequences of electrocardiographic artifact mimicking ventricular tachycardia. N. Engl. J. Med. 1999, 341, 1270–4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
© 2008 by the authors. Attribution - Non-Commercial - NoDerivatives 4.0.