


Case presentation
A 34-year-old primigravida was referred for foetal ultrasound due to irregular heart beat at 31 weeks’ gestation. The foetal echo showed a normal heart and Mmode tracings showed atrioventricular dissociation with an atrial rate of 146 but a ventricular rate of 250. The child was delivered and after birth showed bradycardia with a rate of between 60 and 70. Echo showed normal anatomy and heart function. Except for two episodes of self-limiting torsade-de-pointes type ventricular tachycardia during the first week of life, the baby was clinically stable.
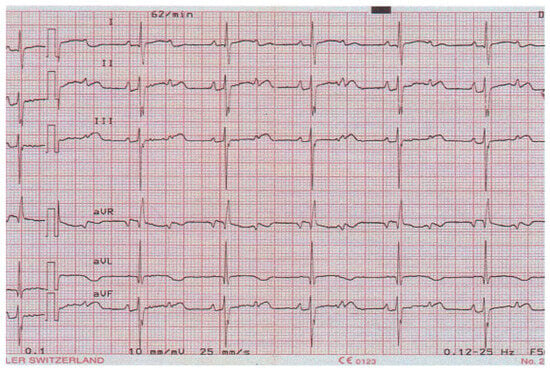
Figure 1 shows the ECG obtained on the third day of life. No specific cardiac drug therapy was given at that time.
Figure 1.
ECG of the neonate on the third day of life; the atrial rate is 124 and the ventricular rate 62. The baby is asleep and haemodynamically stable.
Question
What is the underlying mechanism explaining 2:1 block in this neonate?
Discussion
The ECG shows a regular atrial rate of 124, with every second p-wave situated within the T-wave. The clue to the underlying diagnosis is the measurement of the corrected QT-interval, which is 590 msec (lead II). It is thus a functional 2:1 block with the ventricular myocardium still refractory at the time of the next sinus beat. The diagnosis is long QT syndrome. Foetal or neonatal presentation with an often malignant clinical course is typical of the long QT 3 variant with mutations in the SNC5A gene. The first-line treatment in these babies is pacemaker implantation plus oral betablocker therapy. Our patient received an epicardial left ventricular VVI pacemaker with a rate set at 120 beats, and oral propranolol at 3 mg/kg was started.
This entity has been known for years [1], but so far only a few cases have been reported and show the marked mortality of this condition [1,2]. In recent years this entity has been genetically located and was found to be associated with mutations in the SCN5A gene. No SCN5A gene mutation was found in our patient and no other family members have been found to be affected. Since implantation of the pacemaker, and under oral betablocker treatment, the patient has been well and no further episodes of ventricular tachycardia have been observed.
Conflicts of Interest
There are no conflicts of interest to be declared.
References
- Trippel, D.L.; Parsons, M.K.; Gillette, P.C. Infants with long QT syndrome and 2:1 atrioventricular block. Am. Heart J. 1995, 130, 1130–1134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, C.C.; Acharfi, S.; Wu, M.F.; et al. A novel SCN5A mutation manifests as a malignant form of long QT syndrome with perinatal onset of tachycardia/bradycardia. Cardiovasc. Res. 2004, 64, 268–278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tomek, V.; Skovranek, J.; Gebauer, R.A. Prenatal diagnosis and management of fetal long QT syndrome. Pediatr. Cardiol. 2009, 30, 194–196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
© 2010 by the authors. Attribution - Non-Commercial - NoDerivatives 4.0.