


Abstract
Urinary tract infections (UTIs) are the most prevalent complications in kidney transplant (KTx) recipients. The most frequent finding in this group of patients is asymptomatic bacteriuria (ASB). Here, we provide an overview of the available evidence regarding ASB in KTx recipients, including its etiopathology, clinical impact and management. There is a growing body of evidence from clinical trials that screening for and treating ASB is not beneficial in most KTx recipients. However, there are insufficient data to recommend or discourage the use of a “screen-and-treat strategy” for ASB during the first 1–2 months post-transplant or in the case of an indwelling urinary catheter. Despite its frequency, ASB after KTx is still an understudied phenomenon.
1. Introduction
Urinary tract infections (UTIs) are the most prevalent complications in kidney transplant (KTx) recipients [1,2,3,4,5]. The clinical manifestation or phenotype of symptomatic infections may vary from cystitis to urosepsis. However, a frequent finding in this group of patients is asymptomatic bacteriuria (ASB) [6,7,8,9], which is nowadays considered to be more a form of colonization than infection. The reported prevalence of ASB varies greatly depending on the study, population enrolled, time elapsed since KTx, use of antibiotic prophylaxis and length of follow-up from 3% to 50% [8,10]. ASB is the most frequent clinical phenotype in the first month after KTx, after which symptomatic infections predominate and the relative proportion of ASB decreases [8,11].
2. Definitions
As stated in the guidelines of the Infectious Diseases Society of America (IDSA), ASB is defined in patients without indwelling catheters as the presence of ≥105 colony-forming units (CFU)/mL (≥108 CFU/L) in a voided urine specimen, without coinciding signs or symptoms typical for UTI [12,13,14,15]. For men, a single urine specimen is sufficient for diagnosis, while in women two consecutive specimens should be obtained to confirm the persistence of bacteriuria [16]. This is because in up to 60% of women bacteriuria is transient, and is not present on repeat screening after an initial positive specimen [17,18]. In patients with indwelling devices, the presence of ≥ 105 CFU/mL is still the best diagnostic criterion for bladder bacteriuria [19]. Lower quantitative counts of bacteria (≥102 to <105 CFU/mL) are likely to be a contamination of the urine specimen from the biofilm covering the device rather than true bacteriuria. The presence of from ≥102 to <105 CFU/mL of bacteria in urine specimens collected using “in and out” catheterization or following the placement of a new indwelling catheter points to true bacteriuria, but these lower quantitative counts have undetermined clinical significance in asymptomatic patients. The above listed definitions are true when traditional culture-based methods are used to assess if bacteria are present in the urinary tract. Recent studies using metagenomics have shown that urine is not sterile, as was previously believed, but even in healthy subjects a community of microorganisms termed the microbiome is present [20,21].
3. Etiopathology
Due to the abundance of virulence factors, uropathogenic strains adapted to various ecological niches have acquired the ability to evade the host’s immune response [22]. Polysaccharide capsules, fimbrial and afimbrial adhesins, the iron uptake system (siderophores) and lipopolysaccharides (LPS) are some of the important virulence factors that facilitate bacterial survival and development of infection.
The relationship between UTI and ASB is not well understood. It is possible that the absence of UTI symptoms in the presence of bacteria may follow colonization of the urinary mucosa by defective strains that are unable to induce a full-blown inflammatory response. E. coli, which is the most prevalent uropathogenic strain, has been most extensively studied in this context. However, there is no rigorous molecular definition to differentiate between uropathogenic or merely urocolonizing strains. E. coli strains causing symptomatic infections and ASB showed different virulence gene repertoires. The UTI isolates were more likely to have the papEF and fyuA genes, while the feoB gene was significantly less common than in ASB isolates. The cluster of the virulence gene fimH (+) kpsMTII (+) feoB (+) was significantly more common in ASB strains. Strains causing ASB were also more resistant to a significant proportion of the antimicrobials tested [23]. Rice et al. found that ASB progression to symptomatic infection in KTx recipients was associated with a unique pattern of adherence factors with the expression of P fimbriae but not Dr fimbriae [24]. This finding was confirmed in a prospective study using bacterial whole-genome sequencing to analyze 72 E. coli strains isolated from urine of 54 KTx recipients. In this study, the prevalence of pap genes, i.e., the number of genes required for the production of P fimbriae was significantly higher in E. coli isolates from cases of acute graft pyelonephritis (AGPN) than in cases of ASB [25].
According to Salvador et al., E. coli ASB strains have a reduced virulence potential due to the loss of virulence genes or a lack of expression of genes encoding them. It is likely that long-term colonization of the urinary bladder, especially in hospitalized patients, leads to attenuation of the virulence phenotype as a result of adaptation to the host environment [26]. It was observed that negative expression of fimbriae type 1 and fimbriae type P was a result of partial deletions of the encoding determinants. The authors established that the dominant phylogenetic lineage of ASB was clonal complex 73 (CC73). However, another analyzed line, ST95, was less frequently included in ASB isolates [26]. Some investigators have also reported biofilm formation to be higher in ASB strains [27,28,29,30], but this phenomenon was later questioned [18]. Eberly et al. performed large-scale metabolomic analysis of 300 ASB- and cystitis-associated isolates to find a distinct metabolic signature, especially one related to purine metabolism, differentiating cystitis strains from ASB strains [31].
Gołębiewska et al., who investigated gene profiles encoding virulence factors of K. pneumoniae isolated from KTx recipients with ASB, demonstrated that in ASB isolates the kpn gene encoding FimH-like adhesin was significantly more prevalent as compared with isolates causing symptomatic UTIs. It was shown that the kpn gene may replace the expression of type 1 fimbriae, promoting bacterial colonization and endurance in ASB cases [32].
The host–pathogen interaction in cases of ASB involves not only changes in the expression of bacterial functional virulence factors and metabolism, but also the ability to modulate the host’s immune response to allow the survival and persistence of asymptomatic strains, e.g., by reducing the expression of the host’s immunity-related genes [33]. In another work, K. pneumoniae NDM-1 strains were isolated from KTx recipients, some of them suffered due to UTI and others had ASB or were only colonized. The genetic background of bacteria was examined using WGS (whole genome sequencing). It was found that the strains had high genetic similarity and clonal origin. The profiles of virulence were similar too, regardless of whether they caused only colonization, ASB or UTI. The authors suggested that, for some patients, the innate immune response may not be strong enough to generate symptoms [34]. Asymptomatic colonization of the human bladder by ASB E. coli strain 83,972 has been shown to suppress selected disease-associated signaling pathways [35,36]. Heitmuller et al., using model insect host G. mellonella larvae infected with either uropathogenic or urocolonizing E. coli strains, showed strain-specific differences in the class and expression levels of genes encoding antimicrobial peptides, cytokines and enzymes controlling DNA methylation and histone acetylation [37]. Even though ASB strains are able to prevent the development of a systemic inflammatory reaction, they may still induce a local inflammatory response. In patients with low-grade, papillary, and non-muscle-invasive tumors and chronic ASB the number of recurrences and recurrent tumors was lower, and tumor-free survival times were longer than similarly staged uninfected patients. Therefore, it has been hypothesized that urocolonizing strains may reduce bladder tumor recurrence by activating local immune mechanisms [38]. In KTx recipients, the urine IL-8 level was elevated in both patients with symptomatic UTI and in cases of asymptomatic bacteriuria in comparison to the control group, most probably indicating an ongoing occult inflammatory process in the urinary tract [39].
4. Predisposing Factors
Many pre-, peri- and post-transplant factors are believed to increase the risk of UTIs, including ASB, in KTx recipients. These include female gender, diabetes mellitus, immunosuppression and kidney allograft dysfunction or rejection, underlying urinary tract abnormalities and instrumentation of the urinary tract, including ureteral stent placement and prolonged urinary catheterization. So far, the dose or type of maintenance immunosuppression has not been found to impact the risk of UTIs. Various authors have suggested different potential ASB risk factors. The only consistent finding was the increased risk of ASB in females [8,10,40]. In a study by Coussement et al., female KTx recipients over the age of 50 were the population at highest risk of having ASB [10]. In an analysis of 2363 UTI events recorded in 2368 KTx recipients, including 1111 episodes of ASB, the 1-year incidence of ASB was also significantly higher in females [11]. Notably, an association between the Charlson Comorbidity Index (CCI) [41] and risk of ASB was suggested in one of the studies. While the authors did not find a statistically significant association between risk of ASB and any specific comorbid conditions, they showed that upon multivariate analysis CCI that takes into account a variety of medical conditions, how advanced they are, together with age, also predicting long-term mortality, was a predictor of ASB. [8].
5. Etiology
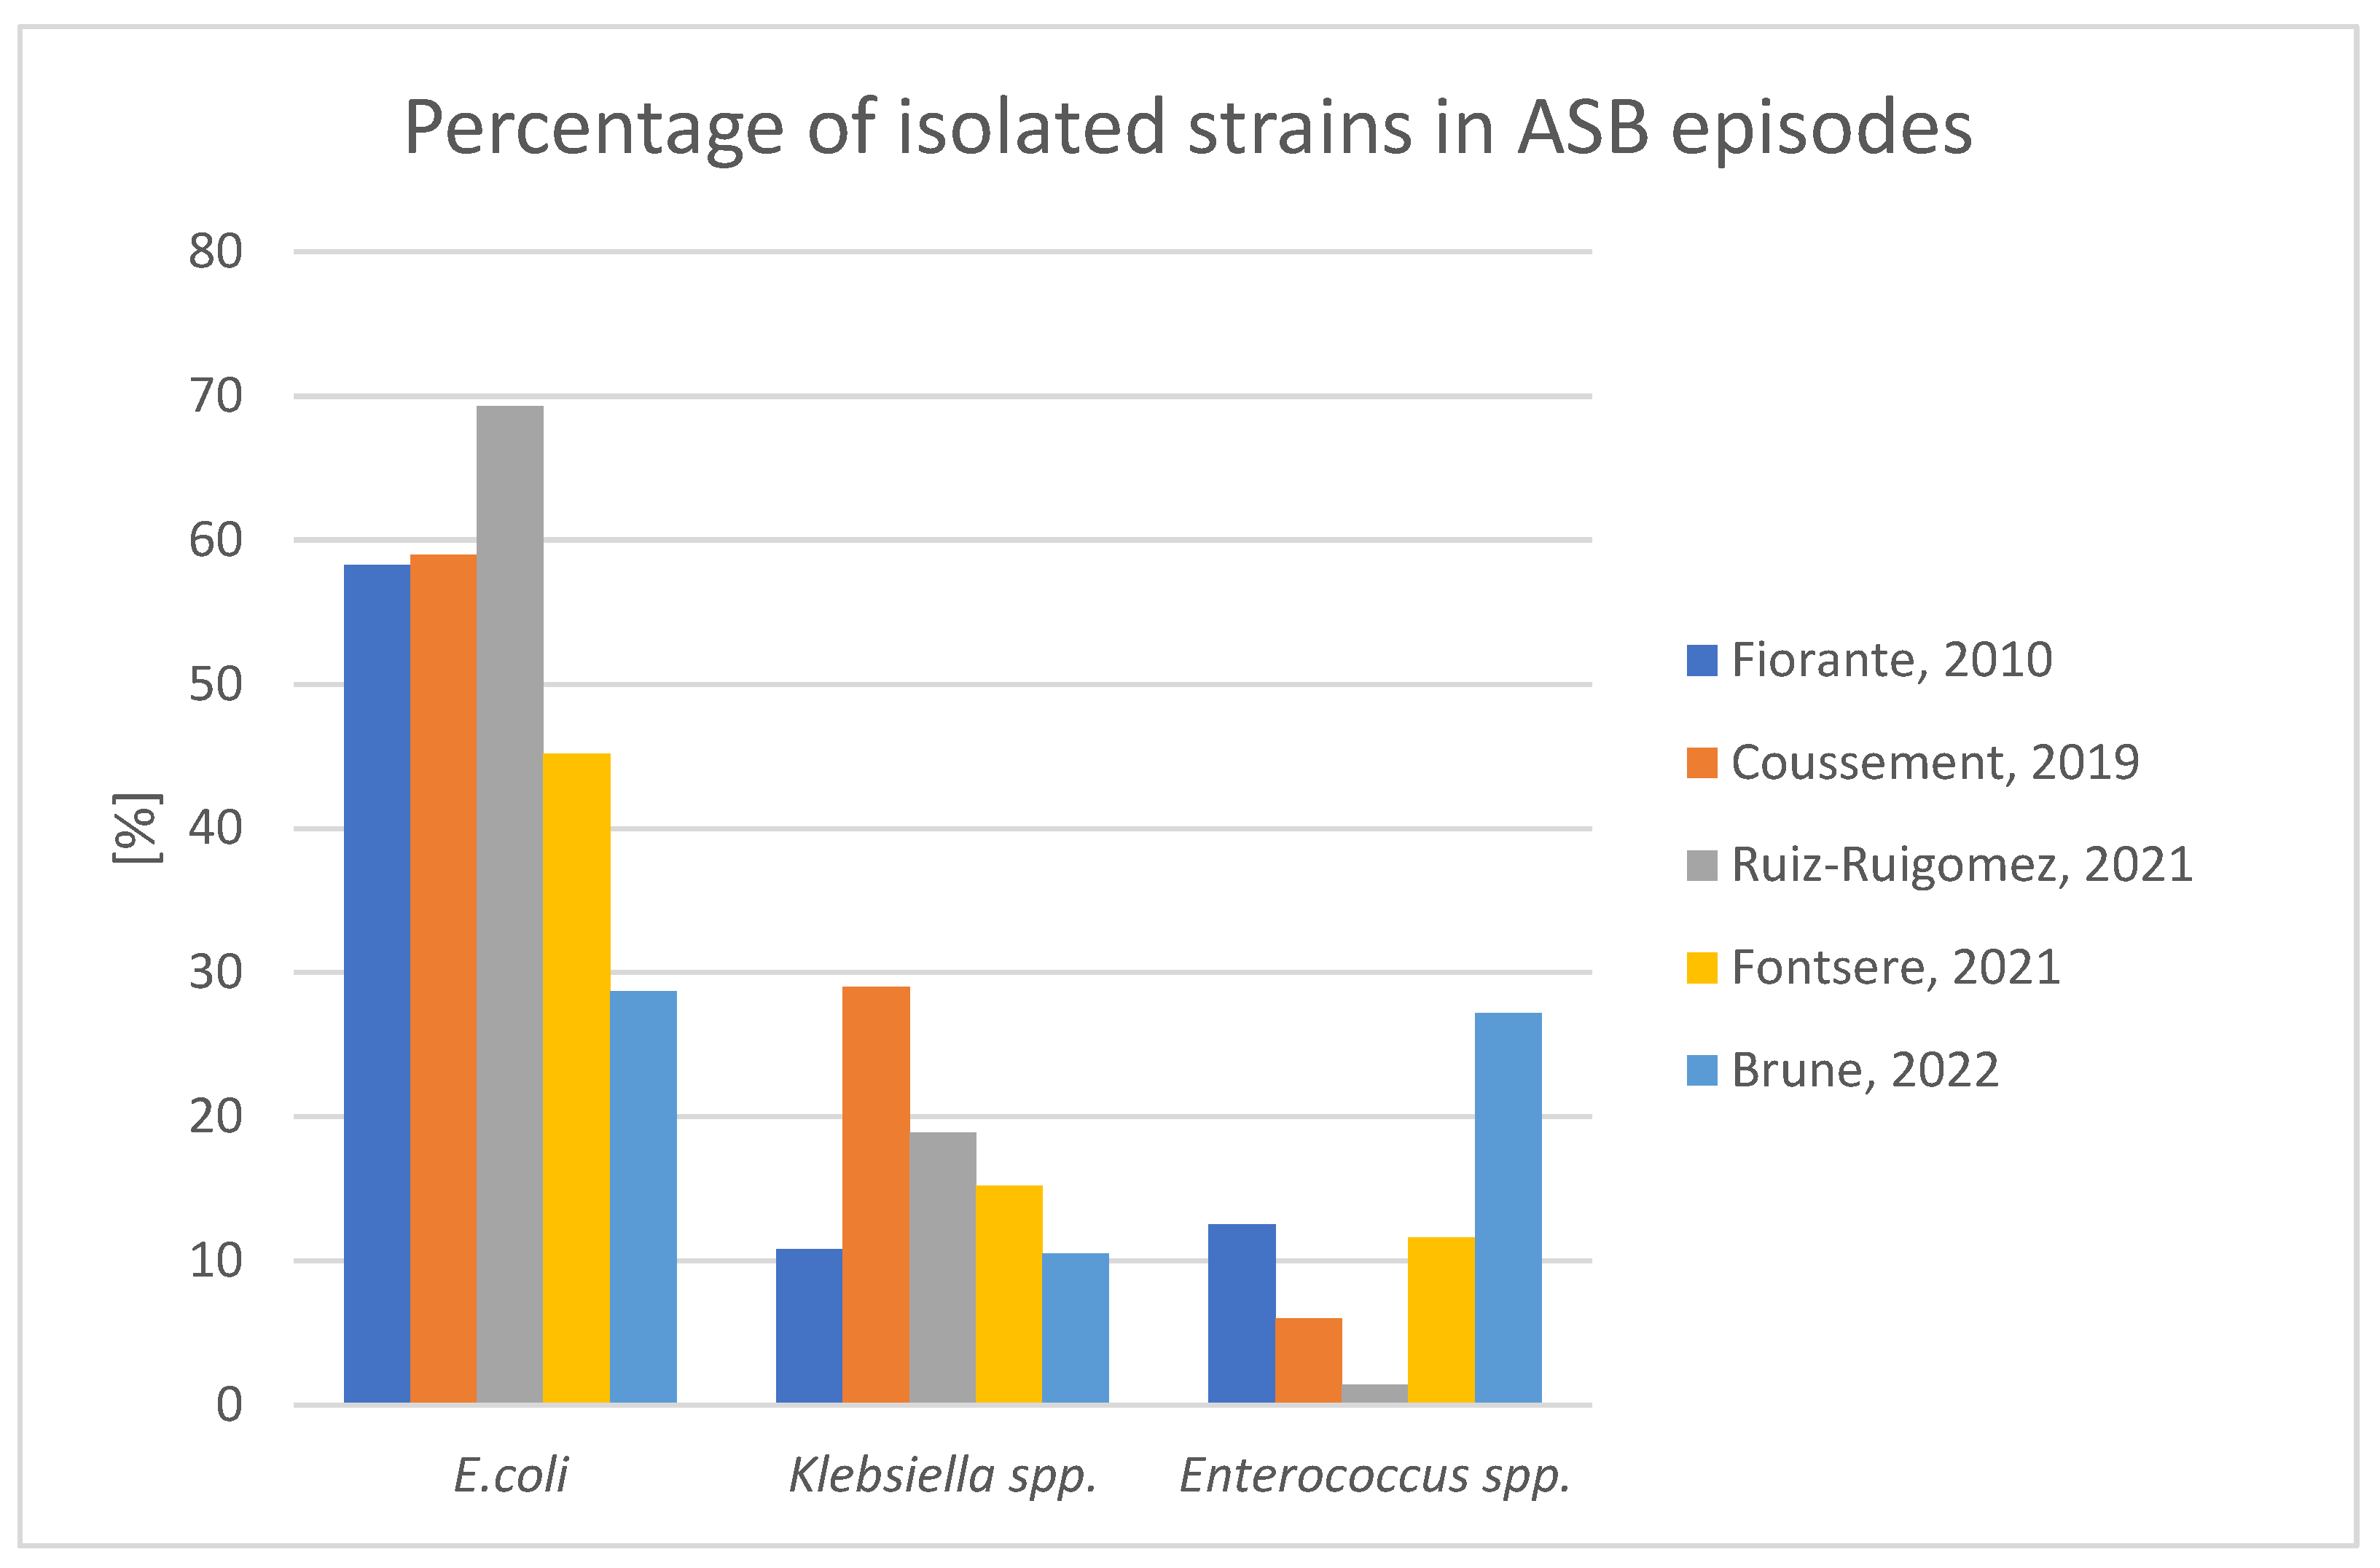
The etiology of ASB mirrors the etiology of symptomatic UTIs, with a predominance of Gram-negative rods typically colonizing the gastrointestinal tract such as E.coli or Klebsiella spp. It is noteworthy that strains isolated early post-KTx differ from those found in late periods after KTx. In a single center study by Gołębiewska et al., in the first month after KTx E. faecium predominated, followed by E. faecalis and E. coli. Beginning from the second month, E. coli was the most frequently isolated urinary pathogen, followed by Proteus species and Klebsiella species [8]. Brune et al., in a multicenter observational study, reported distinct pathogen profiles in ASB compared to UTIs, including urosepsis. Specifically, in ASB the proportion of Enterococcus species and coagulase-negative Staphylococci was significantly higher than in symptomatic infections. The pathogen profile in symptomatic infections included E. coli, Enterococcus species and Klebsiella species, which accounted for about 85% of all causative agents. Notably, the pathogen profiles in all UTI phenotypes remained stable over the first twelve months after KTx and were not affected by either the removal of the double J-stent or the use of prophylaxis with trimethoprim-sulfametoxazole [11]. The frequency of the three most common etiological agents in ASB episodes according to various authors is presented in Figure 1.
Figure 1.
The most common bacteria isolated in asymptomatic bacteriuria episodes according to various authors.
6. Clinical Impact of ASB
At least in theory avoiding UTI in KTx recipient might improve patient and kidney allograft survival. In KTx recipients microorganisms colonizing the lower urinary tract and causing ASB may constitute a hazard for upper urinary tract invasion and development of full-blown symptomatic infection, including urosepsis. In the setting of immunosuppressive therapy, the host’s immune response may not offer a chance for a spontaneous recovery from even a benign infection, especially soon after KTx. The available data on the effect that UTIs have on long-term kidney allograft function are inconclusive. The true influence of various phenotypes of UTIs on both the recipient and kidney allograft outcome has so far not been established. The general belief is that asymptomatic bacteriuria (AB) is benign, in contrast to symptomatic upper UTIs, such as acute graft pyelonephritis or urosepsis. However, even if UTIs do not affect kidney allograft survival directly, they can pose a significant indirect risk by causing bacteraemia, contributing to, e.g., acute rejection.
6.1. Risk of Symptomatic UTI
All published studies analyzed the impact of ASB on the risk of symptomatic UTI development. In retrospective analyses, when all episodes of ASB were treated, ASB was a risk factor for the development of symptomatic UTI. Fiorante et al. showed that the incidence of acute graft pyelonephritis (AGPN) in KTx recipients was seven-fold higher in those with ASB compared with those without ASB. A history of recurrent ASB bacteriuria episodes (either two to five or more than five episodes) was a significant independent factor associated with AGPN [42]. The observations were similar in another retrospective study that included ASB as an independent risk factor for symptomatic UTIs. However, the authors indicated that only a small proportion of symptomatic UTIs were preceded by ASB with the same pathogen and concluded that recurrent ASB episodes may be considered a risk factor, a marker of increased susceptibility to symptomatic infections or a result of repeated and prolonged exposure to antibiotics [8]. When a comparison was made between cases of treated and untreated ASB, it clearly indicated that the risk of developing a symptomatic UTI or a symptomatic UTI requiring hospital admission increased only in those who received antibiotic therapy [43,44]. In pediatric KTx recipients, most untreated ASB episodes resolved without sequelae and on the other hand, most cases of both lower and upper symptomatic UTIs were de novo infections, which developed without preceding ASB [45].
Studies that assessed the prevalence, outcomes and management of asymptomatic bacteriuria (ASB) in KTx recipients are outlined in Table 1.
6.2. Impact on Kidney Allograft Function
A number of studies evaluated the impact of ASB on kidney allograft function. In a study on 189 KTx recipients who were followed for 36 months, which included 96 KTx recipients who developed 298 episodes of ASB, no differences were found in serum creatinine, creatinine clearance or proteinuria between patients with and without ASB [42]. In another retrospective analysis, the evolution of kidney allograft function also did not differ significantly between recipients with and without different UTI phenotypes, including ASB. However, patients suffering from symptomatic UTIs had significantly worse kidney allograft function measured by eGFR from the baseline in comparison with those without UTIs. The eGFR of recipients with a history of only ASB did not differ significantly when compared to both patients with symptomatic infections and patients with no infections [8]. Other studies have confirmed that both one-year patient and graft survival were comparable in recipients with or without ASB [11,44,46]. Furthermore, the antibiotic treatment of ASB did not affect the serum creatinine concentrations at baseline or the end of the study, when compared with the no treatment group [43,46,47,48,49].
6.3. Risk of Acute Rejection
A series of retrospective studies published in the literature have looked at the risk of acute rejection (AR) in KTx patients with ASB [8,40,42,44,46,50]. Fiorante et al. found that multiple ASB episodes were associated with rejection. However, the authors highlighted that not all the episodes of rejection were preceded by ASB episodes, so it was impossible to determine the causality of this relationship [42]. No other study has confirmed this finding regarding the risk for AR occurrence. Moreover, the antibiotic treatment of ASB had no effect on the risk of AR when compared to having no treatment [8,40,44,46,50].
Table 1.
Studies that assessed the prevalence, outcomes and management of asymptomatic bacteriuria (ASB) in KTx recipients.
7. Management
The process of screening for and treating ASB is a common practice in many European kidney transplantation centers [56,57]. Seventy-two percent of European physicians involved in the care of KTx recipients always screen for ASB in their patients, while only 6% never treat ASB [57]. We fear that infections can rapidly progress in immunosuppressed patients and that it may be particularly difficult to distinguish between ASB and a true UTI in the setting of subtle symptoms mitigated by immunosuppression. Even in the general population, where guidelines are clear-cut, antimicrobials are often unnecessarily used to treat cases of ASB, especially in patients with poor functional status and men [58].
On the other hand, the concern for unnecessary treatment of ASB originates from the rapidly growing bacterial resistance and the perception of antibiotic stewardship as a public health priority [59]. UTIs caused by multidrug resistant Gram-negative bacteria are more and more common, especially in the population of solid organ transplant recipients, and are a growing concern due to limited treatment options [60,61].
On an individual level, the unnecessary exposure to antibiotics may be associated with potential side effects, negatively impacting one’s microflora, and, therefore, leading to undesirable consequences such as increasing the risk of colonization or infection by multidrug-resistant bacteria, such as Clostridioides difficile infection, etc.
Whether antibiotic treatment of ASB is in fact helpful or harmful in preventing symptomatic infections in KTx recipients has not been fully elucidated so far. In a study by Cai et al. of a non-transplant population of young women, the treatment of ASB in patients affected by recurrent UTIs resulted in a higher rate of symptomatic UTIs [62]. There is a growing body of evidence from various types of studies showing that screening for and treating ASB is also not beneficial in most KTx recipients. Earlier retrospective studies showed that the incidence of symptomatic UTIs, including AGPN, was higher in KTx recipients with multiple, recurring episodes of ASB, either despite or because of the implemented antibiotic treatment [8,32,44]. At the same time, very few symptomatic UTIs were preceded by ASB with the same causative agent [8]. In a study by Green et al., the use of antibiotics in cases of ASB increased the risk of both symptomatic UTI and a hospital stay [43]. Interestingly, the chance of bacterial clearance was higher in KTx recipients with ASB who received no treatment when compared to those who were administered antibiotics [52]. The findings were similar in pediatric KTx recipients—91.5% of untreated cases of ASB were not followed by a symptomatic UTI and over 80% of cases of AGPN were not preceded by ASB [45]. Only a single study of 185 KTx recipients showed that untreated ASB was significantly more likely to be followed by a subsequent episode of symptomatic UTI in the same organism in comparison to cases of treated ASB [40]. In a recently published study by Ruiz-Ruigomez, which assessed the rate of microbiological eradication after treatment of ASB episodes with fosfomycin, the treatment failure rate exceeded 40% [55]. Moreover, the routine use of trimethoprim-sulfametoxazole prophylaxis did not reduce the prevalence of ASB [53].
To date, the results of four randomized controlled trials investigating the use of antibiotics for the treatment of ASB in KTx recipients have been published [47,48,49,54]. The results were consistent and showed no apparent benefit of systematic screening and treatment of ASB in the populations of patients beyond 2 months post-transplant. The use of antibiotics did not decrease the likelihood of developing a symptomatic UTI, but promoted the emergence of resistant organisms.
Interestingly, in a group of 420 KTx recipients, the isolates from preoperative urine, preoperative urethral swab and postoperative urinary catheter tip cultures also showed poor concordance with the causal organism during an early symptomatic UTI. Thus, perioperative microbiological screening had very limited or no value [63].
As most studies have failed to demonstrate any benefit of the “screen and treat strategy” in terms of incidence of symptomatic UTIs or long-term kidney allograft function, a paradigm shift toward a more conservative approach has occurred in the management of post-transplant ASB. Indeed, most of the more recent guidelines issued by, e.g., the Spanish Society of Clinical Microbiology and Infectious Diseases (SEIMC), the Infectious Diseases Society of America (IDSA), the American Society of Transplantation Infectious Diseases Community of Practice and the European Association of Urology have clearly recommended against screening for or treating ASB beyond the first month post-transplant (Table 2) [13,64,65,66]. Unfortunately, a survey conducted among European transplant nephrologists involved in the care of adult KTx recipients indicated a huge discrepancy between existing guidelines and everyday clinical practice, with most physicians screening for and treating ASB in their patients, even beyond the second month post-KTx [57].
Table 2.
Published guidelines on management of asymptomatic bacteriuria (ASB) in KTx recipients.
The proportion of different clinical manifestations of UTIs differs between early and late periods after KTx, and ASB episodes predominate in the first post-transplant month [8]. However, evidence concerning ASB occurring during the first post-transplant month or in KTx recipients with indwelling urinary catheters is missing, since these episodes were excluded from all published randomized clinical trials [47,48,49,54]. The net state of immunosuppression is highest during the first post-transplant months and decreases thereafter. The presence of indwelling urinary catheters and double-J stents and the highest rate of urologic interventions during this period may increase the risk of progression from ASB to symptomatic UTI, especially given the fact that symptoms of urinary tract infection may be impeded by graft denervation and inflammatory signs may be altered by immunosuppressive medications. Given the abovementioned differences, the recommendation to not screen for and treat ASB may not be applicable during months 1–2 post-transplant. Further studies are needed to evaluate the efficacy and safety of the “screen and treat strategy” in the early post-KTx period.
8. Conclusions
ASB is a common finding in KTx recipients, especially females. Its etiology mirrors the etiology of symptomatic UTIs, with a predominance of Gram-negative rods typically colonizing the gastrointestinal tract. It seems that ASB strains are able to prevent the development of the host’s systemic inflammatory reaction, although they may still induce a local inflammatory response of unrecognized significance. Given that there is no rigorous molecular definition to differentiate between uropathogenic or merely urocolonizing strains, and that KTx recipients are immunocompromised and suffer from numerous urological malformations (vesicoureteral reflux is a permanent symptom after KTx, and KTx recipients are exposed to invasive diagnostic and therapeutic procedures involving the urinary tract, predisposing them to the rapid development of symptomatic, potentially severe infections), it is common practice to screen for and treat ASB episodes. However, there is a growing body of evidence from clinical trials that this strategy is not beneficial in patients more than 2 months post-transplant in terms of symptomatic UTI prevention. In addition, antibiotic treatment of ASB increases antibiotic use and, therefore, promotes the emergence of more resistant strains. As antibiotics for ASB are typically prescribed as a consequence of the positive result of a urine culture, efforts should be made to stop obtaining urine cultures in KTx recipients who have no signs or symptoms of UTI. There is also no clear-cut repercussion of ASB on kidney allograft function prognosis; thus, there is no rationale to support antibiotic use in ASB episodes in patients more than 2 months post-transplant.
Despite its frequency, ASB after KTx is still an understudied phenomenon, especially in recipients who are 1–2 months post-transplant or who have an indwelling urinary catheter. Further randomized studies are required to provide evidence on how a screen-and-treat strategy for ASB would affect clinical outcomes in the early period post-KTx.
Author Contributions
J.E.G. wrote the original draft. B.K., M.W., A.D. and A.D.-Ś assisted on a critical revision of the article for important intellectual content. All authors have given final approval. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Van Delden, C.; Stampf, S.; Hirsch, H.H.; Manuel, O.; Meylan, P.; Cusini, A.; Hirzel, C.; Khanna, N.; Weisser, M.; Garzoni, C.; et al. Burden and Timeline of Infectious Diseases in the First Year After Solid Organ Transplantation in the Swiss Transplant Cohort Study. Clin. Infect. Dis. 2020, 71, e159–e169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Veroux, M.; Giuffrida, G.; Corona, D.; Gagliano, M.; Scriffignano, V.; Vizcarra, D.; Tallarita, T.; Zerbo, D.; Virgilio, C.; Sciacca, A.; et al. Infective Complications in Renal Allograft Recipients: Epidemiology and Outcome. Transplant. Proc. 2008, 40, 1873–1876. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vidal, E.; Torre-Cisneros, J.; Blanes, M.; Montejo, M.; Cervera, C.; Aguado, J.; Len, O.; Carratalá, J.; Cordero, E.; Bou, G.; et al. Bacterial urinary tract infection after solid organ transplantation in the RESITRA cohort. Transpl. Infect. Dis. 2012, 14, 595–603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jackson, K.R.; Motter, J.D.; Bae, S.; Kernodle, A.; Long, J.J.; Werbel, W.; Avery, R.; Durand, C.; Massie, A.B.; Desai, N.; et al. Characterizing the landscape and impact of infections following kidney transplantation. Am. J. Transplant. 2020, 21, 198–207. [Google Scholar] [CrossRef] [Scilit]
- Naik, A.S.; Dharnidharka, V.R.; Schnitzler, M.A.; Brennan, D.C.; Segev, D.L.; Axelrod, D.; Xiao, H.; Kucirka, L.; Chen, J.; Lentine, K.L. Clinical and economic consequences of first-year urinary tract infections, sepsis, and pneumonia in contemporary kidney transplantation practice. Transpl. Int. 2015, 29, 241–252. [Google Scholar] [CrossRef] [Scilit]
- Gołębiewska, J.; Dębska-Ślizień, A.; Komarnicka, J.; Samet, A.; Rutkowski, B. Urinary Tract Infections in Renal Transplant Recipients. Transplant. Proc. 2011, 43, 2985–2990. [Google Scholar] [CrossRef] [Scilit]
- Gołębiewska, J.E.; Dębska-Ślizień, M.A.; Rutkowski, B. Urinary tract infections during the first year after renal transplantation: One center’s experience and a review of the literature. Clin. Transplant. 2014, 28, 1263–1270. [Google Scholar] [CrossRef] [Scilit]
- Gołębiewska, J.E.; Dębska-Ślizień, M.A.; Rutkowski, B. Treated asymptomatic bacteriuria during first year after renal transplantation. Transpl. Infect. Dis. 2014, 16, 605–615. [Google Scholar] [CrossRef] [Scilit]
- Gołębiewska, J.; Tarasewicz, A.; Dębska-Ślizień, A.; Rutkowski, B. Klebsiella spp Urinary Tract Infections During First Year After Renal Transplantation. Transplant. Proc. 2014, 46, 2748–2751. [Google Scholar] [CrossRef] [Scilit]
- Coussement, J.; Scemla, A.; Hougardy, J.-M.; Sberro-Soussan, R.; Amrouche, L.; Catalano, C.; Johnson, J.R.; Abramowicz, D. Prevalence of asymptomatic bacteriuria among kidney transplant recipients beyond two months post-transplant: A multicenter, prospective, cross-sectional study. PLoS ONE 2019, 14, e0221820. [Google Scholar] [CrossRef] [Scilit]
- Brune, J.E.; Dickenmann, M.; Wehmeier, C.; Sidler, D.; Walti, L.; Golshayan, D.; Manuel, O.; Hadaya, K.; Neofytos, D.; Schnyder, A.; et al. Impact of different urinary tract infection phenotypes within the first year post-transplant on renal allograft outcomes. Am. J. Transplant. 2022, 22, 1823–1833. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nicolle, L.E.; Bradley, S.; Colgan, R.; Rice, J.C.; Schaeffer, A.; Hooton, T.M. Infectious Diseases Society of America; American Society of Nephrology; American Geriatric Society. Infectious Diseases Society of America guidelines for the diagnosis and treatment of asymptomatic bacteriuria in adults. Clin. Infect. Dis. 2005, 40, 643–654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nicolle, L.E.; Gupta, K.; Bradley, S.F.; Colgan, R.; DeMuri, G.P.; Drekonja, D.; Eckert, L.O.; Geerlings, S.E.; Köves, B.; Hooton, T.M.; et al. Clinical Practice Guideline for the Management of Asymptomatic Bacteriuria: 2019 Update by the Infectious Diseases Society of Americaa. Clin. Infect. Dis. 2019, 68, 1611–1615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kass, E.H. Pyelonephritis and Bacteriuria: A Major Problem in Preventive Medicine. Ann. Intern. Med. 1962, 56, 46–53. [Google Scholar] [CrossRef] [Scilit]
- Kunin, C.M. Asymptomatic Bacteriuria. Annu. Rev. Med. 1966, 17, 383–406. [Google Scholar] [CrossRef] [Scilit]
- Gleckman, R.; Esposito, A.; Crowley, M.; Natsios, G.A. Reliability of a single urine culture in establishing diagnosis of asymptomatic bacteriuria in adult males. J. Clin. Microbiol. 1979, 9, 596–597. [Google Scholar] [CrossRef] [Scilit]
- Hooton, T.M.; Scholes, D.; Stapleton, A.E.; Roberts, P.L.; Winter, C.; Gupta, K.; Samadpour, M.; Stamm, W.E. A Prospective Study of Asymptomatic Bacteriuria in Sexually Active Young Women. N. Engl. J. Med. 2000, 343, 992–997. [Google Scholar] [CrossRef] [Scilit]
- Nicolle, L.E.; Harding, G.K.M.; Preiksaitis, J.; Ronald, A. The Association of Urinary Tract Infection with Sexual Intercourse. J. Infect. Dis. 1982, 146, 579–583. [Google Scholar] [CrossRef] [Scilit]
- Hooton, T.M.; Bradley, S.F.; Cardenas, D.D.; Colgan, R.; Geerlings, S.E.; Rice, J.C.; Saint, S.; Schaeffer, A.J.; Tambayh, P.A.; Tenke, P.; et al. Diagnosis, Prevention, and Treatment of Catheter-Associated Urinary Tract Infection in Adults: 2009 International Clinical Practice Guidelines from the Infectious Diseases Society of America. Clin. Infect. Dis. 2010, 50, 625–663. [Google Scholar] [CrossRef] [Scilit]
- Rani, A.; Ranjan, R.; McGee, H.S.; Andropolis, K.E.; Panchal, D.V.; Hajjiri, Z.; Brennan, D.C.; Finn, P.W.; Perkins, D.L. Urinary microbiome of kidney transplant patients reveals dysbiosis with potential for antibiotic resistance. Transl. Res. 2016, 181, 59–70. [Google Scholar] [CrossRef] [Scilit]
- Fricke, W.F.; Maddox, C.; Song, Y.; Bromberg, J.S. Human Microbiota Characterization in the Course of Renal Transplantation. Am. J. Transplant. 2014, 14, 416–427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Krawczyk, B.; Wysocka, M.; Michalik, M.; Gołębiewska, J. Urinary Tract Infections Caused by K. pneumoniae in Kidney Transplant Recipients—Epidemiology, Virulence and Antibiotic Resistance. Front. Cell. Infect. Microbiol. 2022, 12, 446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yun, K.W.; Kim, H.Y.; Park, H.K.; Kim, W.; Lim, I.S. Virulence factors of uropathogenic Escherichia coli of urinary tract infections and asymptomatic bacteriuria in children. J. Microbiol. Immunol. Infect. 2014, 47, 455–461. [Google Scholar] [CrossRef] [Scilit]
- Rice, J.C.; Peng, T.; Kuo, Y.-F.; Pendyala, S.; Simmons, L.; Boughton, J.; Ishihara, K.; Nowicki, S.; Nowicki, B.J. Renal Allograft Injury Is Associated with Urinary Tract Infection Caused by Escherichia coli Bearing Adherence Factors. Am. J. Transplant. 2006, 6, 2375–2383. [Google Scholar] [CrossRef] [Scilit]
- Coussement, J.; Argudín, M.A.; Heinrichs, A.; Racapé, J.; De Mendonça, R.; Nienhaus, L.; Le Moine, A.; Roisin, S.; Dodémont, M.; Jacobs, F.; et al. Host and microbial factors in kidney transplant recipients with Escherichia coli acute pyelonephritis or asymptomatic bacteriuria: A prospective study using whole-genome sequencing. Nephrol. Dial. Transplant. 2018, 34, 878–885. [Google Scholar] [CrossRef] [Scilit]
- Salvador, E.; Wagenlehner, F.; Köhler, C.-D.; Mellmann, A.; Hacker, J.; Svanborg, C.; Dobrindt, U. Comparison of Asymptomatic Bacteriuria Escherichia coli Isolates from Healthy Individuals versus Those from Hospital Patients Shows that Long-Term Bladder Colonization Selects for Attenuated Virulence Phenotypes. Infect. Immun. 2012, 80, 668–678. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hancock, V.; Ferriã¨res, L.; Klemm, P. Biofilm formation by asymptomatic and virulent urinary tract infectious Escherichia coli strains. FEMS Microbiol. Lett. 2007, 267, 30–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wullt, B.; Svanborg, C. Deliberate Establishment of Asymptomatic Bacteriuria—A Novel Strategy to Prevent Recurrent UTI. Pathogens 2016, 5, 52. [Google Scholar] [CrossRef] [Scilit]
- Dobrindt, U.; Wullt, B.; Svanborg, C. Asymtomatic Bacteriuria as a Model to Study the Coevolution of Hosts and Bacteria. Pathogens 2016, 5, 21. [Google Scholar] [CrossRef] [Scilit]
- Sundén, F.; Håkansson, L.; Ljunggren, E.; Wullt, B. Escherichia coli 83972 Bacteriuria Protects Against Recurrent Lower Urinary Tract Infections in Patients with Incomplete Bladder Emptying. J. Urol. 2010, 184, 179–185. [Google Scholar] [CrossRef] [Scilit]
- Eberly, A.R.; Beebout, C.J.; Tong, C.M.C.; Van Horn, G.T.; Green, H.D.; Fitzgerald, M.J.; De, S.; Apple, E.K.; Schrimpe-Rutledge, A.C.; Codreanu, S.G.; et al. Defining a Molecular Signature for Uropathogenic versus Urocolonizing Escherichia coli: The Status of the Field and New Clinical Opportunities. J. Mol. Biol. 2019, 432, 786–804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gołębiewska, J.E.; Krawczyk, B.; Wysocka, M.; Ewiak, A.; Komarnicka, J.; Bronk, M.; Rutkowski, B.; Dębska-Ślizień, A. Host and pathogen factors in Klebsiella pneumoniae upper urinary tract infections in renal transplant patients. J. Med. Microbiol. 2019, 68, 382–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hernández, J.G.; Sundén, F.; Connolly, J.; Svanborg, C.; Wullt, B. Genetic Control of the Variable Innate Immune Response to Asymptomatic Bacteriuria. PLoS ONE 2011, 6, e28289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wysocka, M.; Zamudio, R.; Oggioni, M.R.; Gołębiewska, J.; Bronk, M.; Krawczyk, B. Genetic Background and Antibiotic Resistance Profiles of K. pneumoniae NDM-1 Strains Isolated from UTI, ABU, and the GI Tract, from One Hospital in Poland, in Relation to Strains Nationally and Worldwide. Genes 2021, 12, 1285. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ambite, I.; Lutay, N.; Stork, C.; Dobrindt, U.; Wullt, B.; Svanborg, C. Bacterial Suppression of RNA Polymerase II-Dependent Host Gene Expression. Pathogens 2016, 5, 49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lutay, N.; Ambite, I.; Hernandez, J.G.; Rydström, G.; Ragnarsdóttir, B.; Puthia, M.; Nadeem, A.; Zhang, J.; Storm, P.; Dobrindt, U.; et al. Bacterial control of host gene expression through RNA polymerase II. J. Clin. Investig. 2013, 123, 2366–2379. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heitmueller, M.; Billion, A.; Dobrindt, U.; Vilcinskas, A.; Mukherjee, K. Epigenetic Mechanisms Regulate Innate Immunity against Uropathogenic and Commensal-Like Escherichia coli in the Surrogate Insect Model Galleria mellonella. Infect. Immun. 2017, 85, e00336-17. [Google Scholar] [CrossRef] [Scilit]
- Herr, H.; Donat, M. Reduced Recurrence of Low-grade Papillary Bladder Tumors Associated with Asymptomatic Bacteriuria. Urology 2018, 124, 179–182. [Google Scholar] [CrossRef] [Scilit]
- Ciszek, M.; Pączek, L.; Bartłomiejczyk, I.; Mucha, K. Urine Cytokines Profile in Renal Transplant Patients with Asymptomatic Bacteriuria. Transplantation 2006, 81, 1653–1657. [Google Scholar] [CrossRef] [Scilit]
- Kotagiri, P.; Chembolli, D.; Ryan, J.; Hughes, P.; Toussaint, N. Urinary Tract Infections in the First Year Post–Kidney Transplantation: Potential Benefits of Treating Asymptomatic Bacteriuria. Transplant. Proc. 2017, 49, 2070–2075. [Google Scholar] [CrossRef] [Scilit]
- Charlson, M.E.; Pompei, P.; Ales, K.L.; MacKenzie, C.R. A new method of classifying prognostic comorbidity in longitudinal studies: Development and validation. J. Chronic Dis. 1987, 40, 373–383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fiorante, S.; López-Medrano, F.; Lizasoain, M.; Lalueza, A.; Juan, R.S.; Andrés, A.; Otero, J.R.; Morales, J.M.; Aguado, J.M. Systematic screening and treatment of asymptomatic bacteriuria in renal transplant recipients. Kidney Int. 2010, 78, 774–781. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Green, H.; Rahamimov, R.; Goldberg, E.; Leibovici, L.; Gafter, U.; Bishara, J.; Mor, E.; Paul, M. Consequences of treated versus untreated asymptomatic bacteriuria in the first year following kidney transplantation: Retrospective observational study. Eur. J. Clin. Microbiol. Infect. Dis. 2012, 32, 127–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goh, Y.S.B.; Deng, Z.; Cheong, P.S.C.; Raman, L.; Goh, T.H.A.; Vathsala, A.; Tiong, H.Y. Screening for asymptomatic bacteruria at one month after adult kidney transplantation: Clinical factors and implications. Clin. Transplant. 2017, 31, e12954. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonnéric, S.; Maisin, A.; Kwon, T.; Deschênes, G.; Niel, O. Asymptomatic bacteriuria in pediatric kidney transplant recipients: To treat or not to treat? A retrospective study. Pediatr. Nephrol. 2019, 34, 1141–1145. [Google Scholar] [CrossRef] [Scilit]
- Fontserè, S.; Infante-Domínguez, C.; Suárez-Benjumea, A.; Suñer-Poblet, M.; González-Corvillo, C.; Martín-Gutiérrez, G.; Bernal, G.; Pachón, J.; Pachón-Ibáñez, M.; Cordero, E. Impact of Treating Asymptomatic Bacteriuria in Kidney Transplant Recipients: A Prospective Cohort Study. Antibiotics 2021, 10, 218. [Google Scholar] [CrossRef] [Scilit]
- Moradi, M.; Abbasi, M.; Moradi, A.; Boskabadi, A.; Jalali, A. Effect of Antibiotic Therapy on Asymptomatic Bacteriuria in Kidney Transplant Recipients. Urol. J. 2009, 2, 32–35. [Google Scholar] [CrossRef]
- Origüen, J.; López-Medrano, F.; Fernández-Ruiz, M.; Polanco, N.; Gutiérrez, E.; González, E.; Mérida, E.; Ruiz-Merlo, T.; Morales-Cartagena, A.; Asín, M.A.P.; et al. Should Asymptomatic Bacteriuria Be Systematically Treated in Kidney Transplant Recipients? Results from a Randomized Controlled Trial. Am. J. Transplant. 2016, 16, 2943–2953. [Google Scholar] [CrossRef] [Scilit]
- Coussement, J.; Kamar, N.; Matignon, M.; Weekers, L.; Scemla, A.; Giral, M.; Racapé, J.; Alamartine, É.; Mesnard, L.; Kianda, M.; et al. Antibiotics versus no therapy in kidney transplant recipients with asymptomatic bacteriuria (BiRT): A pragmatic, multicentre, randomized, controlled trial. Clin. Microbiol. Infect. 2020, 27, 398–405. [Google Scholar] [CrossRef] [Scilit]
- Bodro, M.; Sanclemente, G.; Lipperheide, I.; Allali, M.; Marco, F.; Bosch, J.; Cofan, F.; Ricart, M.; Esforzado, N.; Oppenheimer, F.; et al. Impact of urinary tract infections on short-term kidney graft outcome. Clin. Microbiol. Infect. 2015, 21, 1104.e1–1104.e8. [Google Scholar] [CrossRef] [Scilit]
- Amari, E.B.E.; Hadaya, K.; Buhler, L.; Berney, T.; Rohner, P.; Martin, P.-Y.; Mentha, G.; van Delden, C. Outcome of treated and untreated asymptomatic bacteriuria in renal transplant recipients. Nephrol. Dial. Transplant. 2011, 26, 4109–4114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arencibia, N.; Agüera, M.; Rodelo-Haad, C.; López, I.; Sánchez-Agesta, M.; Hurtarte, A.; Navarro, M.; Rodríguez-Benot, A. Short-Term Outcome of Untreated Versus Treated Asymptomatic Bacteriuria in Renal Transplant Patients. Transplant. Proc. 2016, 48, 2941–2943. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, R.; Bemelman, F.J.; Hodiamont, C.J.; Idu, M.M.; Berge, I.J.M.T.; Geerlings, S.E. The impact of trimethoprim-sulfamethoxazole as Pneumocystis jiroveci pneumonia prophylaxis on the occurrence of asymptomatic bacteriuria and urinary tract infections among renal allograft recipients: A retrospective before-after study. BMC Infect. Dis. 2016, 16, 90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sabé, N.; Oriol, I.; Melilli, E.; Manonelles, A.; Bestard, O.; Polo, C.; Arcos, I.L.; Perelló, M.; Garcia, D.; Riera, L.; et al. Antibiotic Treatment Versus No Treatment for Asymptomatic Bacteriuria in Kidney Transplant Recipients: A Multicenter Randomized Trial. Open Forum Infect. Dis. 2019, 6, ofz243. [Google Scholar] [CrossRef] [Scilit]
- Ruiz-Ruigómez, M.; Fernández-Ruiz, M.; Silva, J.T.; Vidal, E.; Origüen, J.; Calvo-Cano, A.; Luna-Huerta, E.; Merino, E.; Hernández, D.; Jironda-Gallegos, C.; et al. Efficacy and Safety of Oral Fosfomycin for Asymptomatic Bacteriuria in Kidney Transplant Recipients: Results from a Spanish Multicenter Cohort. Antimicrob. Agents Chemother. 2021, 65, e02267-20. [Google Scholar] [CrossRef] [Scilit]
- Coussement, J.; Nagler, E.V.; Abramowicz, D. Old Habits Die Hard: Screening for and Treating Asymptomatic Bacteriuria After Kidney Transplantation. Am. J. Transplant. 2016, 16, 3301–3302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coussement, J.; Maggiore, U.; Manuel, O.; Scemla, A.; López-Medrano, F.; Nagler, E.V.; Aguado, J.M.; Abramowicz, D.; Adams, B.; Agnelli, C.; et al. Diagnosis and management of asymptomatic bacteriuria in kidney transplant recipients: A survey of current practice in Europe. Nephrol. Dial. Transplant. 2018, 33, 1661–1668. [Google Scholar] [CrossRef] [Scilit]
- Shpunt, Y.; Estrin, I.; Levi, Y.; Saadon, H.; Ben-Yossef, G.; Goldshtein, L.; Klafter, D.; Zilberman-Itskovich, S.; Ben-David, D.; Katz, D.E.; et al. Antimicrobial use for asymptomatic bacteriuria—First, do no harm. Infect. Control. Hosp. Epidemiol. 2020, 42, 37–42. [Google Scholar] [CrossRef] [Scilit]
- Origüen, J.; Fernández-Ruiz, M.; Lopez-Medrano, F.; Ruiz-Merlo, T.; González, E.; Morales, J.; Fiorante, S.; San-Juan, R.; Villa, J.; Orellana, M.Á.; et al. Progressive increase of resistance in Enterobacteriaceae urinary isolates from kidney transplant recipients over the past decade: Narrowing of the therapeutic options. Transpl. Infect. Dis. 2016, 18, 575–584. [Google Scholar] [CrossRef] [Scilit]
- Bader, M.S.; Loeb, M.; Leto, D.; Brooks, A.A. Treatment of urinary tract infections in the era of antimicrobial resistance and new antimicrobial agents. Postgrad. Med. 2019, 132, 234–250. [Google Scholar] [CrossRef] [Scilit]
- Bader, M.S.; Loeb, M.; Brooks, A.A. An update on the management of urinary tract infections in the era of antimicrobial resistance. Postgrad. Med. 2016, 129, 242–258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cai, T.; Mazzoli, S.; Mondaini, N.; Meacci, F.; Nesi, G.; D’elia, C.; Malossini, G.; Boddi, V.; Bartoletti, R. The Role of Asymptomatic Bacteriuria in Young Women with Recurrent Urinary Tract Infections: To Treat or Not to Treat? Clin. Infect. Dis. 2012, 55, 771–777. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, A.; Ahn, S.; Min, S.-K.; Ha, J.; Kim, Y.S.; Ahn, C.; Min, S.-I. Value of perioperative genitourinary screening culture and colonization status in predicting early urinary tract infection after renal transplantation. PLoS ONE 2018, 13, e0196115. [Google Scholar] [CrossRef] [Scilit]
- de Cueto, M.; Aliaga, L.; Alós, J.-I.; Canut, A.; Los-Arcos, I.; Martínez, J.A.; Mensa, J.; Pintado, V.; Rodriguez-Pardo, D.; Yuste, J.R.; et al. Executive summary of the diagnosis and treatment of urinary tract infection: Guidelines of the Spanish Society of Clinical Microbiology and Infectious Diseases (SEIMC). Enferm. Infecc. Microbiol. Clin. 2017, 35, 314–320. [Google Scholar] [CrossRef] [Scilit]
- Goldman, J.D.; Julian, K. Urinary tract infections in solid organ transplant recipients: Guidelines from the American Society of Transplantation Infectious Diseases Community of Practice. Clin. Transplant. 2019, 33, e13507. [Google Scholar] [CrossRef] [Scilit]
- Bonkat, G.; Bartoletti, R.; Bruyère, F.; Cai, T.; Geerlings, S.E.; Köves, B.; Schubert, S.; Wagenlehner, F. Guidelines on Urological Infections; European Association of Urology: Arnhem, The Netherlands, 2021; pp. 1–66. Available online: https://uroweb.org/guideline/urological-infections/ (accessed on 19 September 2022).
- Eckardt, K.U.; Kasiske, B.L.; Zeier, M.G. KDIGO Clinical Practice Guideline for the Care of Kidney Transplant Recipients. Am. J. Transplant. 2009, 9, S1–S155. [Google Scholar] [CrossRef] [Scilit]
- Yamamoto, S.; Ishikawa, K.; Hayami, H.; Nakamura, T.; Miyairi, I.; Hoshino, T.; Hasui, M.; Tanaka, K.; Kiyota, H.; Arakawa, S. JAID/JSC Guidelines for Clinical Management of Infectious Disease 2015 − Urinary tract infection/male genital infection. J. Infect. Chemother. 2017, 23, 733–751. [Google Scholar] [CrossRef] [Scilit]
- Urinary Tract Infection (Lower): Antimicrobial Prescribing NICE Guideline. 2018, pp. 1–41. Available online: www.nice.org.uk/guidance/ng109 (accessed on 19 September 2022).


Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).