


Abstract
Replication stress (RS) is a hallmark of cancer, largely driven by oncogene activation. Due to high levels of RS, cancer cells depend heavily on the RS response mechanisms to avoid DNA damage. This dependency creates a therapeutic opportunity that can be exploited for more effective cancer treatment. This review synthesizes current mechanistic understanding of RS and RS response and further describes how targeted disruption of RS response proteins (ATR, Chk1, Wee1, PARP, RPA) has been used in preclinical and clinical studies. We summarize preclinical and emerging clinical evidence for exploiting RS for radiosensitization, and outline candidate biomarkers and functional assays for patient selection. We also highlight the links between RS, therapy-induced senescence and innate immune activation via the cGAS–STING (cyclic GMP-AMP synthase—Stimulator of Interferon Genes) pathway, and address current challenges and future directions.
Keywords:
replication stress (RS); DNA damage response (DDR); radiosensitization; radiotherapy; ATR; Chk1; Wee1; PARP; RPA; oncogenes 1. Replication Stress and Replication Stress Response
DNA replication is a central biological process that ensures the faithful transmission of the genetic information in the two daughter cells upon cell division. In eukaryotic cells, genomic DNA is replicated only once per cell cycle, in the S phase of interphase, and this process is vital for the growth, development, and maintenance of organisms [1,2]. DNA replication initiates from numerous genomic loci called replication origins. At these sites, the replisome, a complex of multiple proteins containing DNA helicase and DNA polymerase, unwinds the template DNA and synthesizes new DNA on both leading and lagging strands, creating the replication forks. Replication termination is marked by the convergence of replication forks, the disassembly of the replisome, and the resolution of the newly formed DNA molecules [3,4].
The DNA replication machinery encounters many challenges, which can ultimately lead to disruptions in replication fork progression, decreased replication fidelity, and even lethal DNA double-strand breaks (DSBs). Replication stress (RS) is a term that refers to the challenges and obstacles that emerge during the process of DNA replication, causing replication forks to slow or stall. RS is a complex phenomenon, for which there is neither a standard definition nor a specific set of cellular markers to characterize it [5,6]. Various causes, both intracellular and extracellular, can induce RS [7]. To summarize current knowledge, endogenous sources of RS include difficult-to-replicate DNA sequences, abasic sites, misincorporation of ribonucleotides into replicating DNA, DNA-protein crosslinks, replication–transcription conflicts, DNA secondary structures, oncogene activation [8], and nucleotide pool imbalances [9,10,11,12,13,14,15]. Exogenous sources include ultraviolet (UV) and ionizing radiation, as well as DNA-damaging agents, such as alkylating agents, crosslinking agents, and topoisomerase inhibitors [15,16,17]. These stressors trigger cellular responses to stabilize forks and address the DNA damage. The DNA damage response (DDR) and the RS response signalling pathways share many common proteins, and this overlap is important for preventing genomic instability [18,19].
The various factors that pose obstacles to fork progression and cause RS are traditionally believed to act directly cis at replication forks. However, recent findings propose that RS may also manifest independently of active forks, indicating a potential trans-acting role [20]. Additionally, disruptions in DNA repair processes and their products may impede replication, underscoring the diverse sources of RS [7,21,22].
When replication forks stall, e.g., in the presence of DNA damage, the mini-chromosome maintenance (MCM) replicative helicase continues to unwind the parental DNA downstream, revealing single-stranded DNA (ssDNA) [7]. This ssDNA is coated by Replication Protein A (RPA) and represents the signal for the RS Response. Ataxia telangiectasia and Rad3-related (ATR) kinase is recruited to RPA-ssDNA via the ATR-interacting protein (ATRIP) and is activated by the ATR activator Topoisomerase Binding Protein 1 (TOPBP1) [7,23]. Upon activation, ATR phosphorylates a variety of substrates, including checkpoint kinase 1 (Chk1) and histone H2AX. ATR-mediated checkpoint responses stabilize stalled forks and prevent entry into mitosis in the presence of damaged DNA [21,23,24]. However, when RS is enhanced, e.g., in the absence of ATR, and the amount of ssDNA exceeds the amount of RPA, RPA is depleted, leading to fork collapse and generation of DSBs [25]. Subsequent entrance to mitosis with non-replicated damaged DNA causes cell death through mitotic catastrophe. It is worth noting that this only occurs at very high levels of RS, whereas low to mild levels of RS cause genomic instability in cancer cells [26,27,28].
Although the RS response and DDR pathways share several core components, including ATR and Chk1, their outputs are highly context dependent. Functional specificity is primarily dictated by the nature of the initiating lesion and the phase of the cell cycle. In the S phase, when forks stall in the presence of DNA damage, ssDNA coated by RPA acts as the dominant signaling platform triggering the activation of ATR and its downstream effector Chk1. Accumulating evidence shows that ATR is a multifaceted regulator of replication fork stability via a variety of mechanisms: it suppresses new late origin firing to prevent RPA exhaustion, it prevents fork collapse by regulating fork reversal and nuclease activity, stabilizes the replisome, and facilitates fork restart and repair [29]. In contrast, once replication forks collapse and secondary DSBs are generated, signaling shifts towards the activation of Ataxia-telangiectasia mutated (ATM) kinase. The same also applies in the case of DSBs that are directly induced by ionizing radiation.
Despite the fact that the majority of DNA damage is repaired by the DDR pathways, it is likely that some unrepaired lesions can still remain in the DNA template during replication. To address this issue, cells activate the DNA damage tolerance (DDT) pathways. These complex signalling pathways allow DNA replication to proceed, despite the presence of lesions that could otherwise result in replication fork collapse, postponing the need for lesion repair [21,30,31].
This review focuses on the molecular origins of RS in cancer, its impact on DNA damage responses and radiosensitivity, and current therapeutic efforts to exploit replication-stress vulnerabilities—particularly through inhibition of ATR, Chk1, Wee1, and PARP. To define the scope of this review, we performed a structured literature search in PubMed/MEDLINE and ClinicalTrials.gov (for trials) to identify mechanistic, preclinical, and clinical studies relevant to RS, the RS response, and radiosensitization. Search terms included combinations of “replication stress”, “replication stress response”, “ATR inhibition”, “Wee1 inhibition”, “Chk1 inhibition”, “RPA inhibitor”, “fork protection”, “radiosensitization”, “DDR inhibitors”, “oncogene-induced replication stress”, and “clinical trial”. Publications up to November 2025 were considered. Priority was given to primary research articles that elucidate mechanistic links between RS and DDR, as well as translational and clinical studies evaluating DDR inhibitors and RS response-targeting agents alone or in combination with radiotherapy. Reviews were used for background and cross-referencing. Studies were included based on mechanistic relevance, experimental rigor, and translational importance; non-English language papers and case reports were excluded. Additional key references were identified through manual screening of reference lists from recent high-impact review articles. ClinicalTrials.gov entries were used to compile ongoing clinical studies (retrieval date: 30 November 2025), including information on trial phase, status, and available outcomes.
RS in cancer is increasingly recognized not simply as a static feature imposed by oncogenes, but as a dynamic vulnerability that can be therapeutically exploited. Recent studies show that inhibition of key RS response kinases such as ATR, Chk1, or Wee1—which cancer cells depend on to survive under RS—can tip the balance toward mitotic catastrophe, especially when combined with genotoxic therapy or in tumors with high intrinsic RS [32,33]. In the following sections, we will focus on the oncogene-related sources of RS in cancer, and we will explore the potential of targeting proteins of the RS response as a means to increase the sensitivity of cancer cells to radiotherapy.
2. Replication Stress in Cancer: The Role of Oncogenes
Cancer cells show elevated levels of RS in comparison to normal cells, and this contributes to their genomic instability [8,34,35]. A major cause for that is the activation of oncogenes. Overexpression or persistent activation of oncogenes, such as CCNE1 (Cyclin E1) and CCNE2 (Cyclin E2), oncogenic HRAS, and c-Myc, can cause RS by increasing the levels of replication origin firing [36,37]. The various molecular mechanisms of how oncogenes induce replication stress have been extensively reviewed by other groups [8,21,38,39]. In this section, we will summarize the most recent knowledge related to oncogene-induced RS, providing up-to-date data, with an emphasis on key oncogenes.
Cyclin E (Cyclin E1 and Cyclin E2) belongs to the cyclin family of proteins. Cyclin E directly binds to cyclin-dependent kinase 2 (CDK2) and the Cyclin E/CDK 2 complex stimulates the G1-S transition through the retinoblastoma (Rb)—E2F transcription factor pathway [40,41]. Aberrant Cyclin E expression or function has been observed in many cancers. Overexpression of Cyclin E has been found to shorten G1 and force cells into the S phase with an insufficient pool of nucleotides, leading to RS and genomic instability [42]. Two proposed mechanisms behind Cyclin E-induced RS in earlier studies were the increased origin firing and increased replication–transcription encounters. Increased origin firing, meaning many active replication forks, can lead to nucleotide depletion, and, changes in the origin firing density could interfere with the spatial separation of replication and transcription [37,43]. Recent work has shown that Cyclin E can induce RS via a variety of molecular mechanisms: interference with pre-replication complex (pre-RC) assembly, interference with origin licensing, disturbed origin firing, nucleotide pool depletion due to increased origin firing, and replication–transcription conflicts [44,45].
In a similar context, cell division cycle 25 A (Cdc25A—a phosphatase that activates CDK2) overexpression has been linked to accelerated G1-S transition and genomic instability resulting from RS [46,47,48]. Further evidence to support the role of these oncogenes in RS is provided by Neelsen et al., showing that overexpression of Cyclin E and Cdc25A induces replication fork slowing and replication fork reversal [49]. The finding of replication fork slowing is in line with the nucleotide depletion that was shown by Bester et al. [42].
In addition, oncogene activation can directly interfere with the deoxyribonucleotide (dNTP) biosynthesis pathway, causing depletion of the nucleotides that are necessary for DNA replication and therefore posing an obstacle to the progression of replication forks [50]. Bcl2, a major anti-apoptotic protein, causes replication stress in a similar way—by inhibiting the action of ribonucleotide reductase, an enzyme needed for the biosynthesis of dNTPs [51]. These data, in combination with the aforementioned findings, suggest that oncogenes can cause depletion of the dNTP pool that is necessary for DNA replication via two mechanisms: either by increased origin firing or by directly interfering with the dNTP biosynthesis pathway.
c-Myc is another oncogene that has been linked to RS. Activation of c-Myc has been linked to RS and DNA damage, by compromising the DDR pathways and by inducing the production of reactive oxygen species (ROS) [52]. c-Myc has also been found to interact directly with pre-RC components and replication origins [37]. Furthermore, G1-phase shortening by overexpression of Cyclin E and c-Myc, forces entry to S-phase before completion of transcription. This allows origin firing within transcribing genes, which, in turn, leads to replication–transcription conflicts, replication fork collapse, and DSB formation [53]. A recent study by Peripolli et al. proposed a novel mechanism for c-Myc-induced RS. According to this study, an increase in cohesins load on the DNA specifically at CCCTC-binding factor (CTCF) sites, driven by increased MAU2 levels, interferes with the progression of replication forks and causes RS [54].
The RAS family of genes (HRAS, KRAS, and NRAS) encode small GTPases that regulate cell proliferation and survival in response to extracellular signals [55]. Oncogenic HRASG12V has been found to have a negative effect on DNA replication via a variety of mechanisms. It can cause increased origin firing leading to nucleotide depletion, as it has been observed for other oncogenes, it can directly interfere with ribonucleotide reductase, causing nucleotide depletion, and it can also lead to transcription-replication conflicts [39,56]. HRASG12V overexpression in human fibroblasts (BJ fibroblasts) was shown to cause increased oxidative stress, resulting in slowed fork progression [57]. These data build on previous findings, where RAS-induced senescence was linked to increased ROS production. Furthermore, a recent study showed that oncogenic KRASG12V induces RS, and this is attributed to chromatin compaction mediated by H3K27me3 (tri-methylation of lysine 27 on histone H3) and HP1 (heterochromatin protein 1). Interestingly, cells that survived KRASG12V-induced RS exhibited increased ATR expression to ensure replication fork progression under the RS conditions. This ATR-mediated RS tolerance is dependent on Human primase and DNA-directed polymerase (PrimPol), and, while enabling cells to survive the RS, it also contributes to their genomic instability [58]. Recent work underscores that oncogene-driven RS is multifaceted. For example, cancers driven by mutant RAS not only show increased origin firing and nucleotide depletion, but also elevated R-loop formation and transcription-replication conflicts, leading to persistent fork stress and DNA damage. Such stress often engages the fork-protection machinery and checkpoint kinases (ATR/Chk1), making these tumors particularly dependent on RS response pathways and thus more vulnerable to RS-targeting inhibitors [59].
It is worth noting that such data highlight an interesting trade-off between cell survival and genomic instability during the early stages of tumorigenesis. Oncogene activation induces RS [8,60,61]. This oncogene-induced RS triggers an initial response, including DDR activation and oncogene-induced senescence (OIS), that acts as a barrier to tumor development. Some cells, however, acquire RS tolerance mechanisms that allow replication to continue. Such mechanisms may introduce errors, such as the PrimPol-dependent priming in the case of KRASG12V-induced RS, thus promoting genomic instability. This small subset of cells, characterized by increased genomic instability, begins to clonally expand and represent the origin of cancer [58,62,63]. Therefore, while RS tolerance enables cell survival in the face of oncogene-induced RS, it comes at the cost of increased genomic instability, ultimately fuelling the development and progression of cancer.
As mentioned before, unusual DNA secondary structures, like stem-loops and G4-quadruplexes, are a cause of RS. These structures can be observed in common fragile sites, and it has been shown that RS in preneoplastic lesions is frequent within these regions [64].
Although CCNE1, c-Myc, and oncogenic RAS have well-established roles in elevating RS in cancer, they do so through partially distinct mechanisms that help explain tumor-specific vulnerabilities. Cyclin E overexpression primarily drives RS by shortening the G1 phase, excessive origin firing, dNTP depletion, and replication–transcription conflicts. c-Myc, apart from interference with origin firing dynamics and replication–transcription conflicts, additionally promotes ROS production and alters chromatin organization, including cohesin accumulation at CTCF sites, which collectively impair fork progression. In addition to these mechanisms, oncogenic RAS variants further expand the mechanistic landscape of RS by also causing chromatin compaction and engaging tolerance pathways such as PrimPol-mediated repriming. Notably, c-Myc overexpression has been shown to trigger RS rapidly, before any bioenergetic or metabolic changes in the cell, whereas RAS triggers RS with a delayed onset. In fact, the eventual slowing of replication forks in RAS-overexpressing cells coincides with bioenergetic metabolic changes and increased production of ROS [57]. Despite these mechanistic differences, all oncogenic contexts result in elevated RS and enforce a shared dependence on the RS response pathway, particularly the ATR/Chk1/Wee1 axis. More specifically, common downstream features include excessive ssDNA exposure, replication fork collapse or aberrant fork processing, checkpoint kinase activation, and high reliance on DDR and RS response pathways. This convergence provides a strong rationale for targeting RS response proteins across molecularly heterogeneous tumors.
Consistent with this context, a recent mRNA expression study by Guerrero Llobet et al. in 2022 showed that CDC25A, CCNE1, and MYC oncogenes overexpression induces RS in cancer cell lines. Further data derived from cancer patients revealed more amplified oncogenes that trigger replication stress, including, apart from the ones found in cell lines, CCND1, MYB, MOS, ERBB2, and E2F1. The study concluded with a signature of six genes, AT10, DDX27, ZNF48, C8ORF33, MOCS3, and MPP6, which are upregulated in response to oncogene-induced RS. This research provided a very important data pool for investigating the levels of RS in various cancer types [65].
3. Radiotherapy and Cancer Cell Radioresistance
Cancer remains one of the most important challenges in modern medicine and a leading cause of death worldwide. According to the most recent data from the World Health Organization (WHO)/International Agency for Research on Cancer, there were approximately 10 million cancer-related deaths in 2020 globally, and a significant increase in cancer cases worldwide is expected over the next twenty years.
Radiotherapy is a common cancer treatment modality that uses ionizing radiation to kill cancer cells. It is used either alone or often in combination with other therapies, like surgery and chemotherapy. Approximately 50% of cancer patients will receive radiotherapy during the course of their disease [66,67]. Radiotherapy contributes to long-term survival in almost half of cancer patients when combined with other treatment modalities [68]. Radiotherapy is currently used in the treatment of a wide range of solid tumors, including glioblastoma, lung, breast, prostate, colorectal, cervical, esophageal, and head and neck cancers [66,69].
Radioresistance, the development of cancer cell resistance to radiation treatment, is a major challenge to the effectiveness of radiotherapy, contributing to disease progression and poor patient prognosis. Radioresistance can be intrinsic or acquired. Intrinsic radioresistance is present before treatment, while acquired develops during or after radiotherapy [70].
Current studies have shed light on the mechanisms behind radioresistance. The ability of cancer cells to repair the DNA damage caused by radiation is the key factor. In addition, epigenetic mechanisms, like DNA methylation, histone modifications, and non-coding RNAs have been shown to play a role in the development of radioresistance [71,72].
DNA damage from the ionizing radiation used in radiotherapy can be either direct or indirect. In the former type of damage, radiation causes DNA lesions, such as single-strand breaks (SSBs) and DSBs. In the latter type of damage, the absorption of ionizing radiation by the water molecules in the cells generates ROS that cause oxidative damage [73]. DSBs are considered the most lethal type of DNA damage [74]. Actually, it has been shown that ionizing radiation is capable of causing clustered DNA damage—clusters of DNA lesions, all in close proximity, including SSBs, DSBs, oxidized base lesions, as well as regular and oxidized abasic sites [75,76,77]. This complex damage is the major cause of the genomic instability observed in irradiated cancer cells, reduces the effectiveness of the repair mechanisms, and causes cell death [78,79].
Cancer cells, like normal cells, respond to DNA damage caused by ionizing radiation through the DNA damage response and repair (DDR/R) signaling pathways. Enhanced DDR, and thus a higher DNA repair ability, has been observed in radioresistant cancer cells compared to normal cells [80]. This has also been observed in cancer stem-like cells (also referred to as cancer stem cells), a unique subset of tumor cells that have been isolated from leukemias and many types of solid tumors, including glioblastoma, breast cancer, prostate cancer, and melanoma [81,82,83]. Apart from enhanced DDR and cancer stem cells, hypoxia has been identified as another factor that contributes to radioresistance [84].
Based on all the above, targeting components of the DDR/R pathways is considered to be an attractive strategy for improving the effectiveness of chemotherapy and radiotherapy in cancer treatment. The combination of DDR inhibitors with immunotherapy and radiotherapy shows promising results regarding patient prognosis [85,86,87].
4. Targeting Replication Stress for Cancer Treatment and Radiosensitization
Cancer cells depend more on the RS response for their survival than normal cells [21,88]. Enhancing RS by targeting components of the RS response cascades has emerged as a promising approach in cancer therapy, to enhance the genotoxic and cytotoxic effects of chemotherapy and radiotherapy. Thus, small molecule inhibitors of the RS response and DDR cascades can act as radiosensitizers—molecules that potentiate the effectiveness of radiotherapy. In this section, we will summarize the current knowledge and status regarding molecular inhibitors that target major players in the RS response and DDR pathways.
4.1. Targeting ATR/Chk1, the Major Replication Stress Response Mediators
The activation of ATR/Chk1 is crucial for cancer cells to tolerate the enhanced replicative stress and avoid deleterious events such as mitotic catastrophe [89]. Schisandrin B, a natural product, was the first identified potential ATR inhibitor (ATRi), but its clinical application was restricted because of the requirement of a very high dose [90]. A few years later, VE-821, a selective ATRi, was shown to sensitize pancreatic cancer cells to the effects of radiotherapy in vitro [91]. It is worth noting that VE-821 was shown to be an effective radiosensitizer of radioresistant hypoxic tumor cells [92].
AZD6738 (also referred to as ceralasertib) is another potent and specific ATRi. It is orally active and developed by AstraZeneca [93]. The combination of AZD6738 with cisplatin improves the efficacy of cisplatin in ATM-deficient non-small cell lung cancer cells [94]. Furthermore, in a recent phase 1 study, combination of AZD6738 with carboplatin was shown to be well tolerated and presented a moderate clinical benefit for the participating patients [95]. ATRi AZD6738 has also gained particular attention due to its potential to act synergistically with radiotherapy and immunotherapy and improve antitumor immune responses. Vendetti et al. demonstrated that this ATRi enhances the cytotoxic effects of radiation and increases the CD8+ T cell activity in mouse models of KRAS-mutant cancer [96]. In accordance with these results, Sheng et al. also demonstrated that AZD6738 in combination with radiation increases the percentage of tumor-infiltrating CD8+ T cells and reduces the percentage of regulatory T cells in the tumor microenvironment. Triple treatment with AZD6738, radiation, and anti—programmed death-ligand 1 (anti-PD-L1) activated the cGAS-STING signalling pathway and demonstrated promising therapeutic potential in mouse models—it significantly inhibited tumor growth, prolonged survival, and delayed tumor recurrence [97]. Recent preclinical data also show that inhibition of ATR by AZD6738 radiosensitizes prostate cancer cells [98]. Furthermore, a recently published report of the first clinical study combining Ceralasertib with palliative radiotherapy showed that this combination was well tolerated and induced durable responses in patients with solid tumors [99].
Berzosertib (formerly M6620, VX-970, or VE-822) is another highly potent and selective ATRi [100]. Berzosertib has shown promising results in phase 1 clinical trials (NCT02157792, completed in 2020) in patients with advanced solid tumors [101]. Similarly to AZD6738, a recent study by Liu et al. showed that berzosertib enhanced the effects of radiotherapy and immunotherapy, by activating the cGAS-STING pathway and increasing the CD8+ T cell infiltration in mouse colorectal cancer models [102].
The aforementioned studies point to an immunomodulating effect of ATR inhibition in tumors. In accordance, the combination of radiation with AZD6738 or berzosertib has been shown to increase the release of High Mobility Group Box 1 (HMGB1) and the secretion of ATP, which are hallmark factors of immunogenic cell death, in human lung cancer and osteosarcoma cell lines [103]. Further supporting this effect, the combination of ablative radiotherapy with berzosertib was shown to activate the cGAS-STING pathway in lung cancer mouse models, and when combined with anti-PD-L1 it induced immunogenic cell death [104].
Another ATRi, elimusertib (BAY 1895344), has been reported to have a strong anti-tumor activity in lymphomas and to combine well with clinically approved PI3K inhibitor copanlisib in vitro and in vivo [105]. Furthermore, recent preclinical data support the radiosensitizing effect of this ATRi in HPV-negative head and neck squamous cell carcinoma (HNSCC) and in triple negative breast cancer cells [106,107].
Tuvusertib (M1774) is a potent oral ATRi recently evaluated as monotherapy in a first-in-human phase 1 trial in patients with advanced solid tumors, demonstrating manageable safety and exposure-related target engagement. The study supports tuvusertib’s further development and highlights biomarker-guided patient selection and combination strategies [108].
Chk1 is another important target for targeting the RS response. The phosphorylation and subsequent inactivation of Cdc25 by Chk1 is involved in S and G2/M checkpoint controls [109]. Furthermore, inhibition of Chk1 resulted in increased DNA replication initiation, an abnormal increase in ssDNA, and DSBs. These findings support a proposed model in which Chk1 is required for normal S-phase progression by minimizing aberrant initiation of DNA replication [110]. The inhibition of origin firing by Chk1 provides the cell with the necessary time for the resolution of the stress source [93].
The first Chk1 inhibitor that was developed in the 1990s, UCN-01, showed promising preclinical results, but in phase I trials, exhibited limited bioavailability due to high affinity with plasma α1-acid glycoprotein and severe side effects when the dose increased to overcome the bioavailability issue. Since then, more specific inhibitors of Chk1 have been developed. AZD7762 is such an example. It was found to radiosensitize p53 mutant cancer cells, promoting radiation-induced apoptosis in vitro and in xenografts [111,112]. LY2606368 (Prexasertib) and MK-8776 are other Chk1 inhibitors that have been tested in clinical trials, but they have shown limited clinical benefit and occasionally adverse side effects [33,113,114]. In a recent clinical trial (NCT03495323), the combination of Prexasertib with PD-L1 blockade was tolerable and demonstrated preliminary antitumor activity and evidence of cytotoxic T-cell activation in the peripheral blood of patients with high-grade serous ovarian cancer [115]. Furthermore, targeting the ATR/Chk1 axis with a CHK1 inhibitor was shown to significantly sensitize AT-rich interactive domain-containing protein 1A (ARID1A)-deficient colorectal tumors to radiotherapy by triggering cancer cell-intrinsic innate immunity through the cGAS-STING pathway [116].
To date, more than 15 Chk1 inhibitors have progressed into clinical trials, yet none has received marketing authorization [117]. It is worth noting that the severe side effects observed with Chk1 inhibitors reflect the broad role that Chk1 has in the cells, underlining the role of ATR/Chk1 signaling for genome integrity. In a 2025 study, Rawling et al. disclosed BEN-28010, a freely brain-penetrant, potent, and selective Chk1 inhibitor that, when combined with radiation, improved survival in mouse glioblastoma models [118].
4.2. Other Targets
4.2.1. Wee1
Wee1 is a serine/threonine kinase that triggers G2/M arrest by inhibiting CDK1, under conditions of DNA damage. Thus, Wee1 inhibition can induce premature entrance to mitosis without adequate DNA repair [119]. Furthermore, Wee1 inhibition increases origin firing, leading to nucleotide depletion and RS [120,121]. These observations provide the rationale for using Wee1 as a target in cancer treatment: the inhibitors enhance RS in the cells and drive these cells into mitosis, resulting in cell death from mitotic catastrophe.
One such inhibitor is AZD1775 (development code of adavosertib). It has been tested in combination with chemotherapy or radiation, with promising antitumor activity [88]. AZD1775 demonstrated a radiosensitizing ability in various studies [88]. It was shown to radiosensitize hepatocellular carcinoma cells to protons and X-rays, independently of the TP53 status of the cells. The mechanism for that is the induction of RS, as it was proven by the addition of nucleotides that reversed the radiosensitizing effect [122]. Similar results were also observed in esophageal cancer cells [123]. The combination of AZD1775 with chemotherapy and immunotherapy is also under clinical and preclinical investigation [124]. AZD1775 and anti-programmed cell death protein 1 (anti-PD-1) therapy effectively radiosensitize human and mouse hepatoma cells [125].
Recent studies have identified Wee1 as a potential promising therapeutic target in many cancer types characterized by defective checkpoint control. Wee1 inhibition by adavosertib and azenosertib (ZN-c3) selectively induced DNA damage and mitotic catastrophe in ARID1A-deficient, osimertinib-resistant EGFR-mutant non-small cell lung cancer models, while sparing normal fibroblasts, supporting Wee1 targeting as a promising strategy to overcome therapy resistance [126]. Similar results were obtained from a study in ARID1A and TP53 dual-deficient colorectal cancer models, where Wee1 inhibition by MK-1775 or ZN-c3 resulted in pronounced DNA damage and cancer cell death [127]. ATIP3-deficient breast cancer cells are also highly sensitive to Wee1 inhibition, leading to mitotic catastrophe [128]. Importantly, Wee1 targeting has also demonstrated strong radiosensitizing potential. Wee1 inhibition by adavosertib leads to the radiosensitization of glioblastoma cells that are positive for EGFRvIII (epidermal growth factor receptor gene with deletions of exons 2–7), as it was shown in a recent study [129]. It is also worth noting that in HNSCC models, the combined inhibition of Chk1 and Wee1 markedly enhanced radiosensitivity to both X-rays and proton beam therapy [130]. Such results support Chk1/Wee1 inhibition as a promising strategy to sensitize tumors to radiotherapy. The importance of the combination of Wee1 inhibitors with ATR and Chk1 inhibitors is also pointed out by the fact that Wee1 upregulation has been implicated in the development of resistance to ATR and Chk1 inhibitors [131]. Currently, several Wee1 inhibitors are under development because of promising preclinical data [132].
4.2.2. PARP
Poly (ADP-ribose) polymerases (PARPs) are nuclear proteins involved in DDR and they recruit DNA repair proteins to the sites of DSBs. PARP1 also controls fork speed and the choice of RS response mechanisms [133]. PARP inhibition causes RS-induced DNA damage, by preventing replication fork restart [87,88]. Another important characteristic of PARP inhibitors is that they are synthetically lethal in cancer cells with BRCA (Breast Cancer genes) mutations [33,134,135]. Four PARP inhibitors, olaparib, rucaparib, niraparib, and talazoparib, have been approved by the U.S. Food and Drug Administration (FDA) and by the European Medicines Agency (EMA). Olaparib was first approved in 2014 as maintenance therapy for platinum-sensitive advanced ovarian cancer with BRCA1/2 germline mutations [136]. In 2020, the FDA approved olaparib and rucaparib to treat metastatic, castration-resistant prostate cancer, and olaparib was also approved for the treatment of pancreatic cancer [33]. Furthermore, olaparib has been reported to have strong radiosensitizing properties, which have been shown in clinical trials and in cholangiocarcinoma cell lines [137,138]. Emerging evidence indicates that combining RS response inhibitors (ATR and Chk1 inhibitors) with PARP inhibitors can overcome resistance, even in homologous recombination (HR)-proficient tumors. This combination exploits persistent RS and fork protection defects, expanding the therapeutic potential beyond classical BRCA-mutant cancers [139,140]. Furthermore, the combination of PAPR and Wee1 inhibition by olaparib and adavosertib respectively, induces effective radiosensitization of HPV-negative HNSCC cells [141]. A recent study presented a novel series of ATR/PARP1 dual inhibitors, developed by the fusion of AZD6738 and olaparib. One of them, B8, exhibits potent enzymatic activity and synergistic antitumor efficacy in triple-negative breast cancer models [142].
4.2.3. RPA
RPA represents a potential therapeutic target in cancer treatment as it has been shown by some recent studies. HAMNO ((1Z)-1-[(2-hydroxyanilino)methylidene] naphthalen-2-one), TDRL-505, and fumaropimaric acid (NSC15520) are small molecule inhibitors that have been demonstrated to target the RPA70 subunit of RPA in vitro. HAMNO is the most studied one. It has been reported to increase the radiosensitivity of glioblastoma cancer stem-like cells, a very important observation, given that cancer stem-like cells are often radioresistant [143]. A recent study reported no significant changes in the survival of HAMNO-treated irradiated lung carcinoma cells [144], whereas Feng et al. demonstrated that RPA inhibition by HAMNO increased the radiosensitivity of nasopharyngeal carcinoma cells, an important result because radiotherapy is a standard therapeutic approach for nasopharyngeal carcinoma [145]. Our group has used an in silico drug design approach and designed a chemical compound with drug-like properties, targeting the RPA2 subunit and MLH1 [85].
In Table 1, we summarize all current, active clinical trials testing the efficacy and dose schemes of ATR, Chk1, Wee1, and PARP inhibitors.
Table 1.
Current ongoing clinical trials of molecular inhibitors targeting the replication stress response in various cancers. Data retrieved from https://www.clinicaltrials.gov/. Retrieval date: 30 November 2025.
Further supporting the mechanistic link between RS response inhibition and radiosensitization, Wong et al. showed that ATM, ATR, and PARP inhibitors induce markedly greater radiosensitization under fractionated versus single-dose irradiation in breast cancer cells, underscoring the need to test combination strategies in fractionated settings that mirror clinical practice [146].
Beyond the clinically advanced targeting of ATR, Chk1, Wee1, and PARP, which were discussed above, several emerging regulators of RS response and checkpoint control are gaining attention as potential therapeutic targets. For example, TOPBP1, the principal ATR activator, represents an attractive target to selectively disrupt RS responses upstream of ATR. A recent study identified a small-molecule inhibitor targeting TOPBP1, which disrupts TOPBP1 interactions with key partners, exerts antitumor activity, and synergizes with PARP inhibition in preclinical models [147]. MUS81, a nuclease that cuts stalled replication forks to allow restart or repair, also represents a promising target that has not been tested in clinical practice yet [33]. Currently, no selective small molecule MUS81 inhibitors are available, but it has been shown that MUS81-deficient gastric cancer cells are more vulnerable to Wee1 inhibition combined with immune checkpoint blockade therapy [148]. Components of DNA damage tolerance pathways, including RAD18, and the repriming enzyme PrimPol are also emerging targets. Recent evidence indicates that RAD18 contributes to the radioresistance of tumors by enhancing DSB repair [149]. Efforts focus on disrupting the interaction between RAD18 and its stabilizing partner, Melanoma Antigen A4 (MAGE-A4), which is often overexpressed in tumors [150]. This represents a promising approach to destabilize RAD18 and enhance the effects of radiotherapy and chemotherapy. The Ubiquitin-specific protease 1 (USP1) that participates in post-translational modifications of RS response proteins is currently receiving attention as a novel therapeutic target [131]. KSQ-4279 (RO7623066), a selective inhibitor of USP1, has been shown to overcome PARP inhibitor resistance in BRCA-mutant tumors [151]. This inhibitor has been tested in a phase 1 clinical trial (NCT05240898) with promising results. Other USP1 inhibitors, such as SIM0501, XL309–101, and HSK39775, are currently in early phases of clinical development [152]. In parallel, Membrane-associated tyrosine/threonine-protein kinase 1 (PKMYT1, MYT1), a G2/M checkpoint kinase, has recently emerged as a vulnerability in tumors with high levels of RS. When cells face replication stress, MYT1 works alongside Wee1 and phosphorylates CDK1, thus inhibiting it and creating a checkpoint to allow time for repair. Lunresertib is a first-in-class, orally available MYT1 inhibitor that is currently under clinical evaluation [153], (NCT06107868, NCT05605509). Although most of these targets remain at the preclinical or early clinical stage, their mechanistic roles in cellular response to RS provide a strong rationale for combination strategies with radiotherapy or established DDR inhibitors to amplify replication-associated DNA damage and overcome therapy resistance.
5. Replication Stress Biomarkers for Radiosensitivity Prediction
Proteins involved in the RS response pathways represent strong candidates for biomarkers because RS is a commonly observed feature across many cancer types. RS manifests as both molecular and functional defects, which can be quantified using a variety of assays. A pilot study using immunohistochemistry (IHC) on 32 archival formalin-fixed, paraffin-embedded (FFPE) tumor samples (from colon, lung, breast, and stomach cancers) analyzed the expression patterns of five proteins: Ki-67, Cyclin E, POLD3, γH2AX, and FANCD2, concluding that markers widely used in cell line studies require very careful evaluation before being utilized as useful biomarkers in clinical biopsy samples [154]. The accurate identification of tumors with high levels of RS or impaired DDR and RS responses is essential for selecting patients who may benefit from RS inhibition strategies, in combination with radiotherapy (or chemotherapy).
In Table 2, we summarize established and emerging RS biomarkers that may be used to predict tumor response to RS-targeting therapies and radiosensitivity.
Table 2.
RS biomarkers for tumor radiosensitivity prediction.
Because there is no single specific RS marker established, we propose that a combined approach detecting a panel of biomarkers (e.g., combining γH2AX, p-RPA2, and RS-related gene expression) may increase accuracy over single markers for predicting tumor dependency on RS response, radiosensitivity, and therapy response.
In addition to protein- and transcriptomics-based biomarkers, specific genomic alterations related to RS response, DDR, or compromised cell-cycle checkpoint control are emerging as powerful predictors of response to strategies targeting the RS response. For example, a recent study identified that alterations in STK11/LKB1 and/or KEAP1 enhance the antitumor activity of ATR inhibitors in non-small cell lung cancer in vitro and in vivo [164]. In addition, loss of ARID1A, a SWI/SNF chromatin-remodeling factor, leads to elevated RS and impairs the G2/M checkpoint [165], thus rendering ARID1A-deficient tumors selectively vulnerable to Wee1 inhibition. Likewise, TP53 mutations, which disrupt the G1/S checkpoint, enforce dependency on the G2/M checkpoint and sensitize cancer cells to Wee1 and Chk1 inhibition [127,166]. Strong support for genotype-driven patient stratification is provided by recent work from Ng et al., who found that combining radiation with an ATR inhibitor creates a synergistic “synthetic cytotoxicity” specifically in ATM deficient tumors. Beyond ATM, the study identifies a broader panel of 20 genes, such as MCPH1, that sensitize cells to both ionizing radiation and ATR inhibitors [167]. Synthetic lethality between ATR inhibition and ATM deficiency has also been shown previously in gastric cancer cells and other tumors [131,168], as cells with loss of ATM rely only on ATR for orchestrating DDR.
Taken together, the aforementioned data advocate for a biomarker- and genotype-guided patient stratification in RS-targeting and radiosensitization strategies. Integrating genomic profiling with RS-associated protein markers and functional assays is likely to improve patient selection and maximize the therapeutic benefit of RS response inhibition combined with radiotherapy. Given that preclinical and clinical data in this field accumulate continuously, based on current knowledge and taking into account some of the most common genomic alterations in cancers, we propose that for tumors with ATM mutations, ATR inhibitors could be used as radiosensitizers, in tumors with p53 mutations ATR, Wee1, and Chk1 inhibitors could be used as radiosensitizers, and in tumors with BRCA mutations, PARP inhibitors can be prioritized as radiosensitizers.
6. Discussion and Future Perspectives
The interplay between the RS response and the DDR represents a promising research area for the development of novel cancer therapies. Accumulating research and emerging clinical data show that targeting the RS response and the DDR enhances cancer cell sensitivity to DNA damage caused by radiotherapy, primarily by destabilizing stalled replication forks and impairing checkpoint control. The shared components of these pathways, such as ATR and Chk1, have already been targeted in ongoing clinical trials, demonstrating the potential of this approach. It is also worth noting that novel approaches to cancer treatment, combining molecular inhibitors, radiotherapy, and immunotherapy, seem to hold great promise for the future of cancer treatment, taking advantage of their synergistic effects [87].
Cancer cells are relatively more sensitive to RS response and DDR inhibitors than normal cells. A major reason for this is that cancer cells are characterized by elevated intrinsic RS, and therefore, they rely more on the RS response pathway, compared to normal cells [21,88]. This relative tumor selectivity is further reinforced by the frequent defects in cell-cycle control and DDR signaling pathways that characterize cancer cells. For example, high reliance on ATR/Chk1 signaling and deficiencies in ATM, ARID1A, and BRCA1/2 render tumor cells hypersensitive to specific pharmacological inhibitors. In contrast, normal proliferating tissues typically retain intact cell cycle checkpoints and have lower baseline RS.
Intertumoral heterogeneity (between patients with the same tumor type) and intratumoral heterogeneity (within individual tumors) are hallmarks of cancer [169]. In the context of RS, this heterogeneity is reflected in differences in intrinsic RS levels, dependence on RS response pathways, DNA repair capacity, and sensitivity to DDR inhibition [170]. As a result, subclonal populations with distinct DDR defects, replication dynamics, and cell-cycle checkpoint dependencies, are expected to exist in tumors, resulting in heterogeneous responses to ATR, Chk1, Wee1, or PARP inhibition. In the context of radiotherapy, such heterogeneity is also relevant, as subclonal populations with reduced RS or enhanced repair mechanisms may preferentially survive combined treatments, promoting adaptive resistance. Integrating genomic profiling, biomarker-guided approaches, and adaptive treatment strategies may therefore be essential to maximize the antitumor efficacy while limiting resistance arising from tumor heterogeneity.
A major challenge in exploiting RS therapeutically is toxicity to normal proliferating tissues, which rely on intact ATR/Chk1 signaling for genome stability. Consequently, optimizing tolerability is a central challenge in clinical translation. Current knowledge of normal tissue toxicities associated with the use of RS response and DDR inhibitors derives largely from the clinical use of PARP inhibitors, with increasing data emerging for ATR, Chk1, and Wee1 inhibitors. The most commonly reported adverse effects mentioned are hematological and bone marrow toxicities, gastrointestinal disorders, and fatigue [171]. When combined with radiotherapy, the adverse off-target effects may intensify, considering the effects of ionizing radiation on healthy tissues. Furthermore, the combination of DDR inhibitors and chemotherapy has been reported to cause increased bone marrow toxicity, compared to either treatment alone [87]. Several strategies could help mitigate these limitations and improve the therapeutic window. At first, careful planning of dosage and scheduling schemes is required [172]. Short-course administration or intermittent dosing of the RS response inhibitors synchronized with fractions of radiotherapy may also be of benefit. Importantly, the interaction between radiotherapy schedule and inhibitor administration timing is critical, particularly in the context of fractionated radiotherapy, which remains the standard in modern clinical practice [146]. Notably, intermittent dosing and alternating regimens are two strategies that could also help overcome the issue of drug resistance, thus further improving therapeutic efficacy and limiting normal tissue toxicities [173]. Furthermore, sequential rather than fully concurrent treatment schedules may preserve the radiosensitizing effect while reducing damage to normal tissues. In addition, tumor-targeted delivery approaches, such as nanoparticle-based carriers [157], may enhance intratumoral drug accumulation while limiting systemic exposure. Patient selection in oncology is crucial in personalized medicine approaches. Biomarker-driven selection of patients with tumors exhibiting high levels of intrinsic RS can increase the likelihood of enhanced antitumor effects and benefits for the patients. Conversely, biomarkers associated with normal tissue radiosensitivity should also be considered during trial design to minimize the risk of adverse effects [174].
Another major challenge that is increasingly reported is the issue of drug resistance to RS response inhibitors. A well-studied example is resistance to PARP inhibitors, which arises through multiple mechanisms. These include restoration of homologous recombination via reversion mutations or re-expression of homologous recombination genes that were silenced, mutations in PARP1 that decrease PARP trapping, and increased drug efflux via upregulation of specific pumps [131,175]. These adaptive mechanisms can be counteracted by combining PARP inhibition with ATR, Chk1, or Wee1 inhibitors, or even epigenetic drugs [131,176,177]. The main identified mechanisms of resistance to ATR inhibitors are coming from preclinical studies and include loss of Cdc25A, mutations in forkhead box M1 (FOXM1) transcription factor, and mutations in epithelial cell transforming sequence 2 (ECT2) Rho GTPase exchange factor [175]. A novel mechanism identified in gastric cancer involves the loss of UPF2, a component of the nonsense-mediated mRNA decay pathway. Loss of UPF2 reduces transcription-replication collisions, meaning that the cell is less dependent on ATR-mediated fork recovery to survive [178]. Regarding Chk1 inhibitors, recent preclinical data point to Wee1 upregulation as a main mechanism of resistance [179]. In a recent study, Murray et al. showed that tumor-intrinsic PD-L1 determines resistance to Chk1 inhibitors, as PD-L1 depletion enhanced the efficacy of Chk1 inhibitors [180]. Combination and biomarker-based strategies represent an effective means to overcome resistance to RS response inhibitors.
Emerging evidence suggests that RS is not only a driver of genomic instability but can also trigger therapy-induced senescence (TIS) in cancer cells. TIS is a state of cellular senescence (growth arrest) in cancer cells triggered by radiotherapy or chemotherapy [181]. RS contributes to treatment resistance, as it has been shown for glioblastoma. In glioblastoma cell lines, targeting ATR reduced TIS, pushing these cells towards apoptosis. When combined with a PARP-1 inhibitor, ATR inhibition eliminated the senescent cell population even more effectively, highlighting a promising strategy: targeting RS not only to sensitize cells to radiation, but also to target TIS with the potential of better treatment outcomes [182]. Building on this, there is a translational rationale for combining senolytic therapies with RS response inhibition. In triple-negative breast cancer, the combination of PARP inhibition (talazoparib) and irradiation robustly induced senescence, and the subsequent treatment with the senolytic navitoclax (ABT-263) led to apoptosis of the senescent cells and reduced tumor regrowth in vivo [183]. Together, these studies suggest that pushing cells into a senescent state via RS-targeted therapy plus irradiation, and then treating them with senolytics, may have the potential to improve long-term outcomes by eliminating the persistent senescent population. Furthermore, combined targeting of RS and senescence can also be a promising approach. In various lymphoma models, the combination of ATR and PI3K inhibition, by treatment with elimusertib and copanlisib, respectively, has shown in vitro and in vivo antitumor activity [105].
Recent work also highlights how RS can be leveraged to modulate antitumor immunity, particularly through activation of the cGAS-STING pathway. Accumulating preclinical and early clinical data confirms that combining RS response inhibitors with immunotherapy, especially immune checkpoint inhibitors, represents a promising strategy that increases DNA damage and tumor immunogenicity. Cancer cells treated with RS response inhibitors may proceed to mitosis with damaged DNA, leading to cell death via mitotic catastrophe. DNA fragments generated following mitotic catastrophe and/or micronuclei formation are released in the cytoplasm and are sensed by the cGAS-STING pathway. The cGAS-STING pathway senses cytosolic dsDNA, triggering type I interferon signaling, dendritic cell activation, and promoting cytotoxic T-cell infiltration [184,185]. While this pathway is essential for immune recognition, chronic or low-level activation, observed often in tumors with high chromosomal instability and persistent DNA damage, creates an immunosuppressive environment by upregulating PD-L1 expression [186]. This explains the rationale of combining RS response-targeting therapy with anti-PD-L1 immune checkpoint inhibition therapy. In the same context, a recent study demonstrated that enhancing replication stress by Chk1 inhibition can be coupled with anti-PD-1 immunotherapy to improve antitumor responses. It is also noteworthy that the authors developed manganese-based nanoparticles carrying the Chk1 inhibitor PF477736 [187]. As mentioned before, such nanoparticle-based delivery platforms may help widen the therapeutic window by enhancing tumor-selective accumulation of DDR inhibitors, reducing systemic toxicity, and enabling rational multi-modality combinations. A promising multi-modal therapeutic strategy is to combine RS response or DDR inhibitors with radiotherapy and immunotherapy to overcome cancer’s ability to resist single-modality treatments [87]. Finally, it is worth mentioning that computational and “omics”-based approaches are a valuable help in the discovery of potential therapeutic targets in many diseases, including cancers [188,189]. Furthermore, data from these approaches can lead to the identification of new RS-associated targets and predictive biomarkers and also facilitate the design of new inhibitors with drug-like properties. The characterization of specific RS biomarkers can improve the selection of patients who may benefit from RS response-targeting strategies.
7. Concluding Remarks
High levels of RS represent a defining vulnerability of cancer cells that can be exploited to enhance the efficacy of radiotherapy. Targeting RS response pathways promotes replication fork collapse, increases DNA damage burden, and disrupts checkpoint control, thereby amplifying radiation-induced cytotoxicity. The combination of the G2/M checkpoint impairment caused by ATR/Chk1 and Wee1 inhibition, and the DNA damage caused by ionizing radiation, forces cells to enter mitosis prematurely, with unrepaired damaged DNA, leading to mitotic catastrophe. Beyond direct cytotoxic effects, strategies that target the RS response and enhance RS can also induce senescence and generate cytosolic DNA, linking DNA damage to innate immune activation through the cGAS-STING pathway. Emerging approaches combining DDR inhibition with senolytics, immunotherapy, or nanoparticle-based drug delivery offer promising opportunities to improve the therapeutic index and overcome the severe issue of resistance to therapy. Rational patient stratification using RS-associated biomarkers has the potential to increase future clinical success.
Below, we provide a visual summary (Figure 1) of the major concepts covered in this review.
Figure 1.
Schematic overview of replication stress (RS) in cancer cells, RS response, and therapeutic strategies for radiosensitization. (A) Oncogene activation induces replication stress, resulting in stalled replication forks. (B) The ATR/Chk1 pathway is activated in response to replication stress, promoting fork stabilization and cell cycle arrest to maintain genome integrity. (C) Therapeutic inhibition of RS response factors (ATR, Chk1, Wee1, PARP, RPA), combined with ionizing radiation, leads to replication fork collapse and mitotic catastrophe, enhancing radiosensitivity. (D) Emerging strategies: RS response inhibition combined with radiotherapy promotes immunogenic cell death and therapy-induced senescence (TIS), which can subsequently be exploited using senolytic agents. Specific biomarkers like the ones mentioned in this review can help identify patients who will most likely benefit from the aforementioned approaches.
As many RS response inhibitors are currently under preclinical and clinical development, we expect that, in the near future, such strategies will offer benefits to cancer patients.
Author Contributions
Conceptualization, S.N.V. and A.G.G.; investigation, S.N.V. and I.T.; writing—original draft preparation, S.N.V., I.T., I.K.-L., A.G. and A.G.G.; writing—review and editing, A.G.G., S.H., O.E.T., I.K.-L., S.N.V., I.T. and A.G.; visualization, S.N.V., A.G.G., I.T. and I.K.-L.; supervision, A.G.G., I.K.-L., S.H. and O.E.T.; project administration, A.G.G. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ARID1A | AT-rich interactive domain-containing protein 1A |
| ATM | Ataxia-telangiectasia mutated kinase |
| ATR | Ataxia telangiectasia and Rad3-related kinase |
| ATRi | ATR inhibitor |
| ATRIP | ATR-interacting protein |
| BRCA1/2 | Breast cancer genes 1 and 2 |
| Cdc25A | Cell division cycle 25 A |
| cGAS | Cyclic GMP–AMP synthase |
| Chk1 | Checkpoint kinase 1 |
| DDR | DNA damage response |
| DDR/R | DNA damage response and repair |
| DDT | DNA damage tolerance |
| dNTP | deoxyribonucleotide |
| DSBs | DNA double-strand breaks |
| ECT2 | Epithelial cell transforming sequence 2 |
| EGFR | Epidermal growth factor receptor |
| EMA | European Medicines Agency |
| FDA | Food and Drug Administration |
| FOXM1 | Forkhead box M1 transcription factor |
| H3K27me3 | tri-methylation of lysine 27 on histone H3 |
| HMGB1 | High Mobility Group Box 1 |
| HNSCC | Head and neck squamous cell carcinoma |
| HP1 | Heterochromatin protein 1 |
| MAGE-A4 | Melanoma Antigen A4 |
| MCM | Mini-chromosome maintenance (replicative helicase) |
| MYT1 | Membrane-associated tyrosine/threonine-protein kinase 1 |
| OIS | Oncogene-induced senescence |
| PARP | Poly(ADP-ribose) polymerase |
| PD-1 | Programmed cell death protein 1 |
| PD-L1 | Programmed death-ligand 1 |
| PrimPol | Human primase and DNA-directed polymerase |
| ROS | Reactive oxygen species |
| RPA | Replication protein A |
| RS | Replication stress |
| SSBs | Single-strand breaks |
| ssDNA | Single-stranded DNA |
| STING | Stimulator of interferon genes |
| TIS | Therapy-induced senescence |
| TOPBP1 | Topoisomerase-binding protein 1 |
| USP1 | Ubiquitin-specific protease 1 |
| UV | Ultraviolet radiation |
| WHO | World Health Organization |
References
- Gilbert, D.M. Evaluating genome-scale approaches to eukaryotic DNA replication. Nat. Rev. Genet. 2010, 11, 673–684. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siddiqui, K.; On, K.F.; Diffley, J.F.X. Regulating DNA Replication in Eukarya. Cold Spring Harb. Perspect. Biol. 2013, 5, a012930. [Google Scholar] [CrossRef] [Scilit]
- Fragkos, M.; Ganier, O.; Coulombe, P.; Méchali, M. DNA replication origin activation in space and time. Nat. Rev. Mol. Cell Biol. 2015, 16, 360–374. [Google Scholar] [CrossRef] [Scilit]
- Dewar, J.M.; Walter, J.C. Mechanisms of DNA replication termination. Nat. Rev. Mol. Cell Biol. 2017, 18, 507–516. [Google Scholar] [CrossRef] [Scilit]
- Meessen, S.; Najjar, G.; Azoitei, A.; Iben, S.; Bolenz, C.; Günes, C. A Comparative Assessment of Replication Stress Markers in the Context of Telomerase. Cancers 2022, 14, 2205. [Google Scholar] [CrossRef] [Scilit]
- Fouad, S.; Hauton, D.; D’Angiolella, V. E2F1: Cause and Consequence of DNA Replication Stress. Front. Mol. Biosci. 2021, 7, 599332. [Google Scholar] [CrossRef] [Scilit]
- Zeman, M.K.; Cimprich, K.A. Causes and consequences of replication stress. Nat. Cell Biol. 2014, 16, 2–9. [Google Scholar] [CrossRef] [Scilit]
- Halazonetis, T.D.; Gorgoulis, V.G.; Bartek, J. An Oncogene-Induced DNA Damage Model for Cancer Development. Science 2008, 319, 1352–1355. [Google Scholar] [CrossRef] [Scilit]
- Aguilera, A.; García-Muse, T. Causes of Genome Instability. Annu. Rev. Genet. 2013, 47, 1–32. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mendoza, O.; Bourdoncle, A.; Boulé, J.-B.; Brosh, R.M., Jr.; Mergny, J.-L. G-quadruplexes and helicases. Nucleic Acids Res. 2016, 44, 1989–2006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lambert, S.; Carr, A.M. Impediments to replication fork movement: Stabilisation, reactivation and genome instability. Chromosoma 2013, 122, 33–45. [Google Scholar] [CrossRef] [Scilit]
- Koç, A.; Wheeler, L.J.; Mathews, C.K.; Merrill, G.F. Hydroxyurea Arrests DNA Replication by a Mechanism That Preserves Basal dNTP Pools. J. Biol. Chem. 2004, 279, 223–230. [Google Scholar] [CrossRef] [Scilit]
- Donne, R.; Saroul-Ainama, M.; Cordier, P.; Hammoutene, A.; Kabore, C.; Stadler, M.; Nemazanyy, I.; Galy-Fauroux, I.; Herrag, M.; Riedl, T.; et al. Replication stress triggered by nucleotide pool imbalance drives DNA damage and cGAS-STING pathway activation in NAFLD. Dev. Cell 2022, 57, 1728–1741.e6. [Google Scholar] [CrossRef] [Scilit]
- Hamperl, S.; Bocek, M.J.; Saldivar, J.C.; Swigut, T.; Cimprich, K.A. Transcription-Replication Conflict Orientation Modulates R-Loop Levels and Activates Distinct DNA Damage Responses. Cell 2017, 170, 774–786.e19. [Google Scholar] [CrossRef] [Scilit]
- Cybulla, E.; Vindigni, A. Leveraging the replication stress response to optimize cancer therapy. Nat. Rev. Cancer 2023, 23, 6–24. [Google Scholar] [CrossRef] [Scilit]
- Berti, M.; Ray Chaudhuri, A.; Thangavel, S.; Gomathinayagam, S.; Kenig, S.; Vujanovic, M.; Odreman, F.; Glatter, T.; Graziano, S.; Mendoza-Maldonado, R.; et al. Human RECQ1 promotes restart of replication forks reversed by DNA topoisomerase I inhibition. Nat. Struct. Mol. Biol. 2013, 20, 347–354. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lehmann, A.R. Replication of UV-damaged DNA: New insights into links between DNA polymerases, mutagenesis and human disease. Gene 2000, 253, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Mognato, M.; Burdak-Rothkamm, S.; Rothkamm, K. Interplay between DNA replication stress, chromatin dynamics and DNA-damage response for the maintenance of genome stability. Mutat. Res./Rev. Mutat. Res. 2021, 787, 108346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nickoloff, J.A.; Jaiswal, A.S.; Sharma, N.; Williamson, E.A.; Tran, M.T.; Arris, D.; Yang, M.; Hromas, R. Cellular Responses to Widespread DNA Replication Stress. Int. J. Mol. Sci. 2023, 24, 16903. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galanos, P.; Vougas, K.; Walter, D.; Polyzos, A.; Maya-Mendoza, A.; Haagensen, E.J.; Kokkalis, A.; Roumelioti, F.-M.; Gagos, S.; Tzetis, M.; et al. Chronic p53-independent p21 expression causes genomic instability by deregulating replication licensing. Nat. Cell Biol. 2016, 18, 777–789. [Google Scholar] [CrossRef] [Scilit]
- Gorgoulis, V.G.; Pefani, D.-E.; Pateras, I.S.; Trougakos, I.P. Integrating the DNA damage and protein stress responses during cancer development and treatment. J. Pathol. 2018, 246, 12–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saxena, S.; Zou, L. Hallmarks of DNA replication stress. Mol. Cell 2022, 82, 2298–2314. [Google Scholar] [CrossRef] [Scilit]
- Nam, E.A.; Cortez, D. ATR signalling: More than meeting at the fork. Biochem. J. 2011, 436, 527–536. [Google Scholar] [CrossRef] [Scilit]
- Eykelenboom, J.K.; Harte, E.C.; Canavan, L.; Pastor-Peidro, A.; Calvo-Asensio, I.; Llorens-Agost, M.; Lowndes, N.F. ATR Activates the S-M Checkpoint during Unperturbed Growth to Ensure Sufficient Replication Prior to Mitotic Onset. Cell Rep. 2013, 5, 1095–1107. [Google Scholar] [CrossRef] [Scilit]
- Toledo, L.I.; Altmeyer, M.; Rask, M.-B.; Lukas, C.; Larsen, D.H.; Povlsen, L.K.; Bekker-Jensen, S.; Mailand, N.; Bartek, J.; Lukas, J. ATR Prohibits Replication Catastrophe by Preventing Global Exhaustion of RPA. Cell 2013, 155, 1088–1103, Erratum in Cell 2014, 156, 374. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; Dai, Q.; Park, D.; Deng, X. Targeting DNA Replication Stress for Cancer Therapy. Genes 2016, 7, 51. [Google Scholar] [CrossRef] [Scilit]
- Lecona, E.; Fernández-Capetillo, O. Replication stress and cancer: It takes two to tango. Exp. Cell Res. 2014, 329, 26–34. [Google Scholar] [CrossRef] [Scilit]
- Berti, M.; Vindigni, A. Replication stress: Getting back on track. Nat. Struct. Mol. Biol. 2016, 23, 103–109. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blackford, A.N.; Jackson, S.P. ATM, ATR, and DNA-PK: The Trinity at the Heart of the DNA Damage Response. Mol. Cell 2017, 66, 801–817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghosal, G.; Chen, J. DNA damage tolerance: A double-edged sword guarding the genome. Transl. Cancer Res. 2013, 2, 107–129. [Google Scholar]
- Ler, A.A.L.; Carty, M.P. DNA Damage Tolerance Pathways in Human Cells: A Potential Therapeutic Target. Front. Oncol. 2022, 11, 822500. [Google Scholar] [CrossRef] [Scilit]
- Khamidullina, A.I.; Abramenko, Y.E.; Bruter, A.V.; Tatarskiy, V.V. Key Proteins of Replication Stress Response and Cell Cycle Control as Cancer Therapy Targets. Int. J. Mol. Sci. 2024, 25, 1263. [Google Scholar] [CrossRef] [Scilit]
- Nickoloff, J.A. Targeting Replication Stress Response Pathways to Enhance Genotoxic Chemo- and Radiotherapy. Molecules 2022, 27, 4736. [Google Scholar] [CrossRef] [Scilit]
- Taylor, E.M.; Lindsay, H.D. DNA Replication Stress and Cancer: Cause or Cure? Future Oncol. 2016, 12, 221–237. [Google Scholar] [CrossRef] [Scilit]
- Negrini, S.; Gorgoulis, V.G.; Halazonetis, T.D. Genomic instability—An evolving hallmark of cancer. Nat. Rev. Mol. Cell Biol. 2010, 11, 220–228. [Google Scholar] [CrossRef] [Scilit]
- Bartkova, J.; Rezaei, N.; Liontos, M.; Karakaidos, P.; Kletsas, D.; Issaeva, N.; Vassiliou, L.-V.F.; Kolettas, E.; Niforou, K.; Zoumpourlis, V.C.; et al. Oncogene-induced senescence is part of the tumorigenesis barrier imposed by DNA damage checkpoints. Nature 2006, 444, 633–637. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jones, R.M.; Mortusewicz, O.; Afzal, I.; Lorvellec, M.; García, P.; Helleday, T.; Petermann, E. Increased replication initiation and conflicts with transcription underlie Cyclin E-induced replication stress. Oncogene 2013, 32, 3744–3753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Primo, L.M.F.; Teixeira, L.K. DNA replication stress: Oncogenes in the spotlight. Genet. Mol. Biol. 2019, 43, e20190138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kotsantis, P.; Petermann, E.; Boulton, S.J. Mechanisms of Oncogene-Induced Replication Stress: Jigsaw Falling into Place. Cancer Discov. 2018, 8, 537–555. [Google Scholar] [CrossRef] [Scilit]
- Kelly, B.L.; Wolfe, K.G.; Roberts, J.M. Identification of a substrate-targeting domain in cyclin E necessary for phosphorylation of the retinoblastoma protein. Proc. Natl. Acad. Sci. USA 1998, 95, 2535–2540. [Google Scholar] [CrossRef] [Scilit]
- Ohtsubo, M.; Theodoras, A.M.; Schumacher, J.; Roberts, J.M.; Pagano, M. Human Cyclin E, a Nuclear Protein Essential for the G1-to-S Phase Transition. Mol. Cell. Biol. 1995, 15, 2612–2624. [Google Scholar] [CrossRef] [Scilit]
- Bester, A.C.; Roniger, M.; Oren, Y.S.; Im, M.M.; Sarni, D.; Chaoat, M.; Bensimon, A.; Zamir, G.; Shewach, D.S.; Kerem, B. Nucleotide Deficiency Promotes Genomic Instability in Early Stages of Cancer Development. Cell 2011, 145, 435–446. [Google Scholar] [CrossRef] [Scilit]
- Petrakis, T.G.; Komseli, E.-S.; Papaioannou, M.; Vougas, K.; Polyzos, A.; Myrianthopoulos, V.; Mikros, E.; Trougakos, I.P.; Thanos, D.; Branzei, D.; et al. Exploring and exploiting the systemic effects of deregulated replication licensing. Semin. Cancer Biol. 2016, 37–38, 3–15, Erratum in Semin. Cancer Biol. 2017, 43, 180. [Google Scholar] [CrossRef] [Scilit]
- Fagundes, R.; Teixeira, L.K. Cyclin E/CDK2: DNA Replication, Replication Stress and Genomic Instability. Front. Cell Dev. Biol. 2021, 9, 774845. [Google Scholar] [CrossRef] [Scilit]
- Ekholm-Reed, S.; Méndez, J.; Tedesco, D.; Zetterberg, A.; Stillman, B.; Reed, S.I. Deregulation of cyclin E in human cells interferes with prereplication complex assembly. J. Cell Biol. 2004, 165, 789–800. [Google Scholar] [CrossRef] [Scilit]
- Blomberg, I.; Hoffmann, I. Ectopic Expression of Cdc25A Accelerates the G1/S Transition and Leads to Premature Activation of Cyclin E- and Cyclin A-Dependent Kinases. Mol. Cell. Biol. 1999, 19, 6183–6194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cangi, M.G.; Cukor, B.; Soung, P.; Signoretti, S.; Moreira, G., Jr.; Ranashinge, M.; Cady, B.; Pagano, M.; Loda, M. Role of the Cdc25A phosphatase in human breast cancer. J. Clin. Investig. 2000, 106, 753–761. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guerrero Llobet, S.; van der Vegt, B.; Jongeneel, E.; Bense, R.D.; Zwager, M.C.; Schröder, C.P.; Everts, M.; Fehrmann, R.S.N.; de Bock, G.H.; van Vugt, M.A.T.M. Cyclin E expression is associated with high levels of replication stress in triple-negative breast cancer. NPJ Breast Cancer 2020, 6, 40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neelsen, K.J.; Zanini, I.M.Y.; Herrador, R.; Lopes, M. Oncogenes induce genotoxic stress by mitotic processing of unusual replication intermediates. J. Cell Biol. 2013, 200, 699–708. [Google Scholar] [CrossRef] [Scilit]
- Aird, K.M.; Zhang, G.; Li, H.; Tu, Z.; Bitler, B.G.; Garipov, A.; Wu, H.; Wei, Z.; Wagner, S.N.; Herlyn, M.; et al. Suppression of Nucleotide Metabolism Underlies the Establishment and Maintenance of Oncogene-Induced Senescence. Cell Rep. 2013, 3, 1252–1265. [Google Scholar] [CrossRef] [Scilit]
- Xie, M.; Yen, Y.; Owonikoko, T.K.; Ramalingam, S.S.; Khuri, F.R.; Curran, W.J.; Doetsch, P.W.; Deng, X. Bcl2 Induces DNA Replication Stress by Inhibiting Ribonucleotide Reductase. Cancer Res. 2014, 74, 212–223. [Google Scholar] [CrossRef] [Scilit]
- Vafa, O.; Wade, M.; Kern, S.; Beeche, M.; Pandita, T.K.; Hampton, G.M.; Wahl, G.M. c-Myc Can Induce DNA Damage, Increase Reactive Oxygen Species, and Mitigate p53 Function: A Mechanism for Oncogene-Induced Genetic Instability. Mol. Cell 2002, 9, 1031–1044. [Google Scholar] [CrossRef] [Scilit]
- Macheret, M.; Halazonetis, T.D. Intragenic origins due to short G1 phases underlie oncogene-induced DNA replication stress. Nature 2018, 555, 112–116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peripolli, S.; Meneguello, L.; Perrod, C.; Singh, T.; Patel, H.; Rahman, S.T.; Kiso, K.; Thorpe, P.; Calvanese, V.; Bertoli, C.; et al. Oncogenic c-Myc induces replication stress by increasing cohesins chromatin occupancy in a CTCF-dependent manner. Nat. Commun. 2024, 15, 1579. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.J.; Lee, H.N.; Jeong, M.S.; Jang, S.B. Oncogenic KRAS: Signaling and Drug Resistance. Cancers 2021, 13, 5599. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Micco, R.; Fumagalli, M.; Cicalese, A.; Piccinin, S.; Gasparini, P.; Luise, C.; Schurra, C.; Garre’, M.; Nuciforo, P.G.; Bensimon, A.; et al. Oncogene-induced senescence is a DNA damage response triggered by DNA hyper-replication. Nature 2006, 444, 638–642. [Google Scholar] [CrossRef] [Scilit]
- Maya-Mendoza, A.; Ostrakova, J.; Kosar, M.; Hall, A.; Duskova, P.; Mistrik, M.; Merchut-Maya, J.M.; Hodny, Z.; Bartkova, J.; Christensen, C.; et al. Myc and Ras oncogenes engage different energy metabolism programs and evoke distinct patterns of oxidative and DNA replication stress. Mol. Oncol. 2015, 9, 601–616. [Google Scholar] [CrossRef] [Scilit]
- Igarashi, T.; Mazevet, M.; Yasuhara, T.; Yano, K.; Mochizuki, A.; Nishino, M.; Yoshida, T.; Yoshida, Y.; Takamatsu, N.; Yoshimi, A.; et al. An ATR-PrimPol pathway confers tolerance to oncogenic KRAS-induced and heterochromatin-associated replication stress. Nat. Commun. 2023, 14, 4991. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Técher, H.; Kemiha, S.; Aobuli, X.; Kolinjivadi, A.M. Oncogenic RAS in Cancers from the DNA Replication Stress and Senescence Perspective. Cancers 2024, 16, 3993. [Google Scholar] [CrossRef] [Scilit]
- Zampetidis, C.P.; Galanos, P.; Angelopoulou, A.; Zhu, Y.; Polyzou, A.; Karamitros, T.; Kotsinas, A.; Lagopati, N.; Mourkioti, I.; Mirzazadeh, R.; et al. A recurrent chromosomal inversion suffices for driving escape from oncogene-induced senescence via subTAD reorganization. Mol. Cell 2021, 81, 4907–4923.e8. [Google Scholar] [CrossRef] [Scilit]
- Gorgoulis, V.G.; Vassiliou, L.-V.F.; Karakaidos, P.; Zacharatos, P.; Kotsinas, A.; Liloglou, T.; Venere, M.; DiTullio, R.A.; Kastrinakis, N.G.; Levy, B.; et al. Activation of the DNA damage checkpoint and genomic instability in human precancerous lesions. Nature 2005, 434, 907–913. [Google Scholar] [CrossRef] [Scilit]
- Kakiuchi, N.; Ogawa, S. Clonal expansion in non-cancer tissues. Nat. Rev. Cancer 2021, 21, 239–256. [Google Scholar] [CrossRef] [Scilit]
- Igarashi, T.; Yano, K.; Endo, S.; Shiotani, B. Tolerance of Oncogene-Induced Replication Stress: A Fuel for Genomic Instability. Cancers 2024, 16, 3507. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsantoulis, P.K.; Kotsinas, A.; Sfikakis, P.P.; Evangelou, K.; Sideridou, M.; Levy, B.; Mo, L.; Kittas, C.; Wu, X.R.; Papavassiliou, A.G.; et al. Oncogene-induced replication stress preferentially targets common fragile sites in preneoplastic lesions. A genome-wide study. Oncogene 2008, 27, 3256–3264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guerrero Llobet, S.; Bhattacharya, A.; Everts, M.; Kok, K.; van der Vegt, B.; Fehrmann, R.S.N.; van Vugt, M.A.T.M. An mRNA expression-based signature for oncogene-induced replication-stress. Oncogene 2022, 41, 1216–1224. [Google Scholar] [CrossRef] [Scilit]
- Baskar, R.; Lee, K.A.; Yeo, R.; Yeoh, K.W. Cancer and radiation therapy: Current advances and future directions. Int. J. Med. Sci. 2012, 9, 193–199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toy, H.I.; Karakülah, G.; Kontou, P.I.; Alotaibi, H.; Georgakilas, A.G.; Pavlopoulou, A. Investigating Molecular Determinants of Cancer Cell Resistance to Ionizing Radiation Through an Integrative Bioinformatics Approach. Front. Cell Dev. Biol. 2021, 9, 620248. [Google Scholar] [CrossRef] [Scilit]
- Huang, R.-X.; Zhou, P.-K. DNA damage response signaling pathways and targets for radiotherapy sensitization in cancer. Signal Transduct. Target. Ther. 2020, 5, 60. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Deng, W.; Li, N.; Neri, S.; Sharma, A.; Jiang, W.; Lin, S.H. Combining Immunotherapy and Radiotherapy for Cancer Treatment: Current Challenges and Future Directions. Front. Pharmacol. 2018, 9, 185. [Google Scholar] [CrossRef] [Scilit]
- Cabrera-Licona, A.; Pérez-Añorve, I.X.; Flores-Fortis, M.; Moral-Hernández, O.d.; González-de la Rosa, C.H.; Suárez-Sánchez, R.; Chávez-Saldaña, M.; Aréchaga-Ocampo, E. Deciphering the epigenetic network in cancer radioresistance. Radiother. Oncol. 2021, 159, 48–59. [Google Scholar] [CrossRef] [Scilit]
- Smits, K.M.; Melotte, V.; Niessen, H.E.C.; Dubois, L.; Oberije, C.; Troost, E.G.C.; Starmans, M.H.W.; Boutros, P.C.; Vooijs, M.; van Engeland, M.; et al. Epigenetics in radiotherapy: Where are we heading? Radiother. Oncol. 2014, 111, 168–177. [Google Scholar] [CrossRef] [Scilit]
- Podralska, M.; Ciesielska, S.; Kluiver, J.; van den Berg, A.; Dzikiewicz-Krawczyk, A.; Slezak-Prochazka, I. Non-Coding RNAs in Cancer Radiosensitivity: MicroRNAs and lncRNAs as Regulators of Radiation-Induced Signaling Pathways. Cancers 2020, 12, 1662. [Google Scholar] [CrossRef] [Scilit]
- Azzam, E.I.; Jay-Gerin, J.-P.; Pain, D. Ionizing radiation-induced metabolic oxidative stress and prolonged cell injury. Cancer Lett. 2012, 327, 48–60. [Google Scholar] [CrossRef] [Scilit]
- Malkova, A.; Haber, J.E. Mutations Arising During Repair of Chromosome Breaks. Annu. Rev. Genet. 2012, 46, 455–473. [Google Scholar] [CrossRef] [Scilit]
- Tremi, I.; Havaki, S.; Georgitsopoulou, S.; Terzoudi, G.; Lykakis, I.N.; Iliakis, G.; Georgakilas, V.; Gorgoulis, V.G.; Georgakilas, A.G. Biological Response of Human Cancer Cells to Ionizing Radiation in Combination with Gold Nanoparticles. Cancers 2022, 14, 5086. [Google Scholar] [CrossRef] [Scilit]
- Hada, M.; Georgakilas, A.G. Formation of Clustered DNA Damage after High-LET Irradiation: A Review. J. Radiat. Res. 2008, 49, 203–210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Borrego-Soto, G.; Ortiz-Lopez, R.; Rojas-Martinez, A. Ionizing radiation-induced DNA injury and damage detection in patients with breast cancer. Genet. Mol. Biol. 2015, 38, 420–432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alexandros, G.G.; Peter, O.N.; Robert, D.S. Induction and Repair of Clustered DNA Lesions: What Do We Know So Far? Radiat. Res. 2013, 180, 100–109. [Google Scholar] [CrossRef] [Scilit]
- Aziz, K.; Nowsheen, S.; Pantelias, G.; Iliakis, G.; Gorgoulis, V.G.; Georgakilas, A.G. Targeting DNA damage and repair: Embracing the pharmacological era for successful cancer therapy. Pharmacol. Ther. 2012, 133, 334–350. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galeaz, C.; Totis, C.; Bisio, A. Radiation Resistance: A Matter of Transcription Factors. Front. Oncol. 2021, 11, 662840. [Google Scholar] [CrossRef] [Scilit]
- Schatton, T.; Murphy, G.F.; Frank, N.Y.; Yamaura, K.; Waaga-Gasser, A.M.; Gasser, M.; Zhan, Q.; Jordan, S.; Duncan, L.M.; Weishaupt, C.; et al. Identification of cells initiating human melanomas. Nature 2008, 451, 345–349. [Google Scholar] [CrossRef] [Scilit]
- Vlashi, E.; Pajonk, F. Cancer stem cells, cancer cell plasticity and radiation therapy. Semin. Cancer Biol. 2015, 31, 28–35. [Google Scholar] [CrossRef] [Scilit]
- Morgan, M.A.; Canman, C.E. Replication Stress: An Achilles’ Heel of Glioma Cancer Stem–like Cells. Cancer Res. 2018, 78, 6713–6716. [Google Scholar] [CrossRef] [Scilit]
- Willers, H.; Azzoli, C.G.; Santivasi, W.L.; Xia, F. Basic Mechanisms of Therapeutic Resistance to Radiation and Chemotherapy in Lung Cancer. Cancer J. 2013, 19, 200–207. [Google Scholar] [CrossRef] [Scilit]
- Vasilopoulos, S.N.; Güner, H.; Uça Apaydın, M.; Pavlopoulou, A.; Georgakilas, A.G. Dual Targeting of DNA Damage Response Proteins Implicated in Cancer Radioresistance. Genes 2023, 14, 2227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nikitaki, Z.; Hellweg, C.E.; Georgakilas, A.G.; Ravanat, J.-L. Stress-induced DNA damage biomarkers: Applications and limitations. Front. Chem. 2015, 3, 35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qiu, Y.; Hu, X.; Zeng, X.; Wang, H. Triple kill: DDR inhibitors, radiotherapy and immunotherapy leave cancer cells with no escape. Acta Biochim. Biophys. Sin. 2022, 54, 1569–1576. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Wu, L.; Wang, Z.; Wang, J.; Roychoudhury, S.; Tomasik, B.; Wu, G.; Wang, G.; Rao, X.; Zhou, R. Replication Stress: A Review of Novel Targets to Enhance Radiosensitivity-From Bench to Clinic. Front. Oncol. 2022, 12, 838637. [Google Scholar] [CrossRef] [Scilit]
- Zhu, H.; Swami, U.; Preet, R.; Zhang, J. Harnessing DNA Replication Stress for Novel Cancer Therapy. Genes 2020, 11, 990. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nishida, H.; Tatewaki, N.; Nakajima, Y.; Magara, T.; Ko, K.M.; Hamamori, Y.; Konishi, T. Inhibition of ATR protein kinase activity by schisandrin B in DNA damage response. Nucleic Acids Res. 2009, 37, 5678–5689. [Google Scholar] [CrossRef] [Scilit]
- Prevo, R.; Fokas, E.; Reaper, P.M.; Charlton, P.A.; Pollard, J.R.; McKenna, W.G.; Muschel, R.J.; Brunner, T.B. The novel ATR inhibitor VE-821 increases sensitivity of pancreatic cancer cells to radiation and chemotherapy. Cancer Biol. Ther. 2012, 13, 1072–1081, Erratum in Cancer Biol. Ther. 2025, 37, 2602376. [Google Scholar] [CrossRef] [Scilit]
- Pires, I.M.; Olcina, M.M.; Anbalagan, S.; Pollard, J.R.; Reaper, P.M.; Charlton, P.A.; McKenna, W.G.; Hammond, E.M. Targeting radiation-resistant hypoxic tumour cells through ATR inhibition. Br. J. Cancer 2012, 107, 291–299. [Google Scholar] [CrossRef] [Scilit]
- Weber, A.M.; Ryan, A.J. ATM and ATR as therapeutic targets in cancer. Pharmacol. Ther. 2015, 149, 124–138. [Google Scholar] [CrossRef] [Scilit]
- Vendetti, F.P.; Lau, A.; Schamus, S.; Conrads, T.P.; O’Connor, M.J.; Bakkenist, C.J. The orally active and bioavailable ATR kinase inhibitor AZD6738 potentiates the anti-tumor effects of cisplatin to resolve ATM-deficient non-small cell lung cancer in vivo. Oncotarget 2015, 6, 44289–44305. [Google Scholar] [CrossRef] [Scilit]
- Yap, T.A.; Krebs, M.G.; Postel-Vinay, S.; El-Khouiery, A.; Soria, J.-C.; Lopez, J.; Berges, A.; Cheung, S.Y.A.; Irurzun-Arana, I.; Goldwin, A.; et al. Ceralasertib (AZD6738), an Oral ATR Kinase Inhibitor, in Combination with Carboplatin in Patients with Advanced Solid Tumors: A Phase I Study. Clin. Cancer Res. 2021, 27, 5213–5224. [Google Scholar] [CrossRef] [Scilit]
- Vendetti, F.P.; Karukonda, P.; Clump, D.A.; Teo, T.; Lalonde, R.; Nugent, K.; Ballew, M.; Kiesel, B.F.; Beumer, J.H.; Sarkar, S.N.; et al. ATR kinase inhibitor AZD6738 potentiates CD8+ T cell–dependent antitumor activity following radiation. J. Clin. Investig. 2018, 128, 3926–3940. [Google Scholar] [CrossRef] [Scilit]
- Sheng, H.; Huang, Y.; Xiao, Y.; Zhu, Z.; Shen, M.; Zhou, P.; Guo, Z.; Wang, J.; Wang, H.; Dai, W.; et al. ATR inhibitor AZD6738 enhances the antitumor activity of radiotherapy and immune checkpoint inhibitors by potentiating the tumor immune microenvironment in hepatocellular carcinoma. J. Immunother. Cancer 2020, 8, e000340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Campen, N.; Mekers, V.E.; Looman, M.W.; van den Bogaard, L.; Kers-Rebel, E.D.; Peeters, W.J.M.; Merino, E.F.; Schuurmans, F.; Smeenk, R.J.; Verheij, M.; et al. ATM and ATR inhibition increases radiosensitivity and cGAS-STING activation in prostate cancer. Cytokine 2025, 193, 156980. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dillon, M.T.; Patin, E.C.; Mohammed, K.; Guevara, J.; Smith, S.A.; Dean, E.; Soliman, H.; Nenclares, P.; Ryugenji, M.; Northcote, D.; et al. Tumor control and immune activation through palliative irradiation and ATR inhibition, PATRIOT Part C: A phase Ib trial. Nat. Commun. 2025, 16, 7064. [Google Scholar] [CrossRef] [Scilit]
- Fokas, E.; Prevo, R.; Pollard, J.R.; Reaper, P.M.; Charlton, P.A.; Cornelissen, B.; Vallis, K.A.; Hammond, E.M.; Olcina, M.M.; Gillies McKenna, W.; et al. Targeting ATR in vivo using the novel inhibitor VE-822 results in selective sensitization of pancreatic tumors to radiation. Cell Death Dis. 2012, 3, e441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Middleton, M.R.; Dean, E.; Evans, T.R.J.; Shapiro, G.I.; Pollard, J.; Hendriks, B.S.; Falk, M.; Diaz-Padilla, I.; Plummer, R. Phase 1 study of the ATR inhibitor berzosertib (formerly M6620, VX-970) combined with gemcitabine ± cisplatin in patients with advanced solid tumours. Br. J. Cancer 2021, 125, 510–519. [Google Scholar] [CrossRef] [Scilit]
- Liu, C.; Wang, X.; Qin, W.; Tu, J.; Li, C.; Zhao, W.; Ma, L.; Liu, B.; Qiu, H.; Yuan, X. Combining radiation and the ATR inhibitor berzosertib activates STING signaling and enhances immunotherapy via inhibiting SHP1 function in colorectal cancer. Cancer Commun. 2023, 43, 435–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eek Mariampillai, A.; Hauge, S.; Kongsrud, K.; Syljuåsen, R.G. Immunogenic cell death after combined treatment with radiation and ATR inhibitors is dually regulated by apoptotic caspases. Front. Immunol. 2023, 14, 1138920. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, J.L.-Y.; Pan, C.-K.; Lin, L.-C.; Huang, Y.-S.; Huang, T.-H.; Yang, S.-J.; Kuo, S.-H.; Lin, Y.-L. Combination of ataxia telangiectasia and Rad3-related inhibition with ablative radiotherapy remodels the tumor microenvironment and enhances immunotherapy response in lung cancer. Cancer Immunol. Immunother. 2024, 74, 8. [Google Scholar] [CrossRef] [Scilit]
- Sartori, G.; Tarantelli, C.; Spriano, F.; Gaudio, E.; Cascione, L.; Mascia, M.; Barreca, M.; Arribas, A.J.; Licenziato, L.; Golino, G.; et al. The ATR inhibitor elimusertib exhibits anti-lymphoma activity and synergizes with the PI3K inhibitor copanlisib. Br. J. Haematol. 2024, 204, 191–205. [Google Scholar] [CrossRef] [Scilit]
- Guney Eskiler, G.; Halis, H.; Hamarat, K.F.; Derlioglu, R.R.; Ugurlu, B.T.; Haciefendi, A. The ATR inhibition by Elimusertib enhances the radiosensitivity of MDA-MB-231 triple negative breast cancer in vitro. Int. J. Radiat. Biol. 2024, 100, 715–723. [Google Scholar] [CrossRef] [Scilit]
- Odhiambo, D.A.; Pittman, A.N.; Rickard, A.G.; Castillo, R.J.; Bassil, A.M.; Chen, J.; Ravotti, M.L.; Xu, E.S.; Himes, J.E.; Daniel, A.R.; et al. Preclinical Evaluation of the ATR Inhibitor BAY 1895344 as a Radiosensitizer for Head and Neck Squamous Cell Carcinoma. Int. J. Radiat. Oncol. Biol. Phys. 2024, 118, 1315–1327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yap, T.A.; Tolcher, A.W.; Plummer, R.; Mukker, J.K.; Enderlin, M.; Hicking, C.; Grombacher, T.; Locatelli, G.; Szucs, Z.; Gounaris, I.; et al. First-in-Human Study of the Ataxia Telangiectasia and Rad3-Related (ATR) Inhibitor Tuvusertib (M1774) as Monotherapy in Patients with Solid Tumors. Clin. Cancer Res. 2024, 30, 2057–2067. [Google Scholar] [CrossRef] [Scilit]
- Zhao, H.; Watkins, J.L.; Piwnica-Worms, H. Disruption of the checkpoint kinase 1/cell division cycle 25A pathway abrogates ionizing radiation-induced S and G2 checkpoints. Proc. Natl. Acad. Sci. USA 2002, 99, 14795–14800. [Google Scholar] [CrossRef] [Scilit]
- Syljuåsen, R.G.; Sørensen, C.S.; Hansen, L.T.; Fugger, K.; Lundin, C.; Johansson, F.; Helleday, T.; Sehested, M.; Lukas, J.; Bartek, J. Inhibition of Human Chk1 Causes Increased Initiation of DNA Replication, Phosphorylation of ATR Targets, and DNA Breakage. Mol. Cell. Biol. 2005, 25, 3553–3562. [Google Scholar] [CrossRef] [Scilit]
- Mitchell, J.B.; Choudhuri, R.; Fabre, K.; Sowers, A.L.; Citrin, D.; Zabludoff, S.D.; Cook, J.A. In vitro and In vivo Radiation Sensitization of Human Tumor Cells by a Novel Checkpoint Kinase Inhibitor, AZD7762. Clin. Cancer Res. 2010, 16, 2076–2084. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, Z.; Yao, G.; Zhou, B.; Fan, Y.; Gao, S.; Feng, X. The Chk1 inhibitor AZD7762 sensitises p53 mutant breast cancer cells to radiation in vitro and in vivo. Mol. Med. Rep. 2012, 6, 897–903. [Google Scholar] [CrossRef] [Scilit]
- Byers, L.A.; Navarro, A.; Schaefer, E.; Johnson, M.; Özgüroğlu, M.; Han, J.-Y.; Bondarenko, I.; Cicin, I.; Dragnev, K.H.; Abel, A.; et al. A Phase II Trial of Prexasertib (LY2606368) in Patients With Extensive-Stage Small-Cell Lung Cancer. Clin. Lung Cancer 2021, 22, 531–540. [Google Scholar] [CrossRef] [Scilit]
- Thompson, R.; Eastman, A. The cancer therapeutic potential of Chk1 inhibitors: How mechanistic studies impact on clinical trial design. Br. J. Clin. Pharmacol. 2013, 76, 358–369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Do, K.T.; Manuszak, C.; Thrash, E.; Giobbie-Hurder, A.; Hu, J.; Kelland, S.; Powers, A.; de Jonge, A.; Shapiro, G.I.; Severgnini, M. Immune modulating activity of the CHK1 inhibitor prexasertib and anti-PD-L1 antibody LY3300054 in patients with high-grade serous ovarian cancer and other solid tumors. Cancer Immunol. Immunother. 2021, 70, 2991–3000. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.-Y.; Ke, T.-W.; Chiang, S.-F.; Hong, W.-Z.; Chang, H.-Y.; Liang, J.-A.; Tsai, Y.-Y.; Huang, C.-H.; Chen, W.T.-L.; Chao, K.S.C.; et al. CHK1 inhibition increases the therapeutic response to radiotherapy via antitumor immunity in ARID1A-deficient colorectal cancer. Cell Death Dis. 2025, 16, 584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, T.; Su, M.; Wang, Y.; Gao, A.; Jiang, K.; Xu, L.; Li, J. A patent review of CHK1 inhibitors (2019–present). Expert Opin. Ther. Pat. 2025, 35, 915–931. [Google Scholar] [CrossRef] [Scilit]
- Rawling, M.J.; Ray-Sinha, A.; Bestwick, M.; Carter, M.K.; Chahal, S.K.; Chalmers, A.J.; Elsey, D.J.; Giddings, A.; Gold, J.; Henderson, S.H.; et al. Discovery of a Potent, Selective, and Brain-Penetrant Checkpoint Kinase 1 Inhibitor, BEN-28010, for the Treatment of Glioblastoma. J. Med. Chem. 2025, 68, 9101–9125. [Google Scholar] [CrossRef] [Scilit]
- Matheson, C.J.; Venkataraman, S.; Amani, V.; Harris, P.S.; Backos, D.S.; Donson, A.M.; Wempe, M.F.; Foreman, N.K.; Vibhakar, R.; Reigan, P. A WEE1 Inhibitor Analog of AZD1775 Maintains Synergy with Cisplatin and Demonstrates Reduced Single-Agent Cytotoxicity in Medulloblastoma Cells. ACS Chem. Biol. 2016, 11, 921–930, Erratum in ACS Chem. Biol. 2016, 11, 2066–2067. [Google Scholar] [CrossRef] [Scilit]
- Moiseeva, T.N.; Qian, C.; Sugitani, N.; Osmanbeyoglu, H.U.; Bakkenist, C.J. WEE1 kinase inhibitor AZD1775 induces CDK1 kinase-dependent origin firing in unperturbed G1- and S-phase cells. Proc. Natl. Acad. Sci. USA 2019, 116, 23891–23893. [Google Scholar] [CrossRef] [Scilit]
- Beck, H.; Nähse-Kumpf, V.; Larsen, M.S.Y.; O’Hanlon, K.A.; Patzke, S.; Holmberg, C.; Mejlvang, J.; Groth, A.; Nielsen, O.; Syljuåsen, R.G.; et al. Cyclin-Dependent Kinase Suppression by WEE1 Kinase Protects the Genome through Control of Replication Initiation and Nucleotide Consumption. Mol. Cell. Biol. 2012, 32, 4226–4236. [Google Scholar] [CrossRef] [Scilit]
- Cuneo, K.C.; Morgan, M.A.; Davis, M.A.; Parcels, L.A.; Parcels, J.; Karnak, D.; Ryan, C.; Liu, N.; Maybaum, J.; Lawrence, T.S. Wee1 Kinase Inhibitor AZD1775 Radiosensitizes Hepatocellular Carcinoma Regardless of TP53 Mutational Status Through Induction of Replication Stress. Int. J. Radiat. Oncol. Biol. Phys. 2016, 95, 782–790. [Google Scholar] [CrossRef] [Scilit]
- Yang, J.; Liu, X.; Cao, S.; Dong, X.; Rao, S.; Cai, K. Understanding Esophageal Cancer: The Challenges and Opportunities for the Next Decade. Front. Oncol. 2020, 10, 1727. [Google Scholar] [CrossRef] [Scilit]
- Kong, A.; Mehanna, H. WEE1 Inhibitor: Clinical Development. Curr. Oncol. Rep. 2021, 23, 107. [Google Scholar] [CrossRef] [Scilit]
- Yin, Y.; Wang, J.; Yi, J.; Zhang, K.; Yin, Z.; Jin, S.; Zheng, B. AZD1775 and anti-PD-1 antibody synergistically sensitize hepatoma to radiotherapy. Chin. Med. J. 2024, 137, 222–231. [Google Scholar] [CrossRef] [Scilit]
- Fukuda, K.; Nanjo, S.; Takeuchi, S.; Chakrabarti, T.; Brown, T.; Dev Sahadevan, S.W.; Arai, S.; Sato, S.; Kotani, H.; Nishiyama, A.; et al. Targeting WEE1 to Overcome ARID1A Mutation-Driven Osimertinib Resistance in EGFR-Mutant Lung Cancer. J. Thorac. Oncol. 2025, 20, 1459–1474. [Google Scholar] [CrossRef] [Scilit]
- Zhang, C.; Zhu, Y.; Ai, L.; Wang, J.; Yu, S.; Wang, Y.; Xu, X.; Liu, M.; Yu, Y.; Zhu, M.; et al. Targeting WEE1 in ARID1A/TP53 Concurrent Mutant Colorectal Cancer by Exploiting RLoop Accumulation and DNA Repair Deficiencies. Adv. Sci. 2025, e12074. [Google Scholar] [CrossRef] [Scilit]
- Haykal, M.M.; Rodrigues-Ferreira, S.; El Botty, R.; Sourd, L.; Marangoni, E.; Varin, M.; Denis, A.; Nahmias, C. Targeting WEE1 kinase as a therapeutic strategy in ATIP3-deficient breast cancers. Cancer Lett. 2025, 620, 217665. [Google Scholar] [CrossRef] [Scilit]
- Cetin, M.H.; Rieckmann, T.; Hoffer, K.; Riepen, B.; Christiansen, S.; Gatzemeier, F.; Feyerabend, S.; Schoof, M.; Schüller, U.; Petersen, C.; et al. G2 checkpoint targeting via Wee1 inhibition radiosensitizes EGFRvIII-positive glioblastoma cells. Radiat. Oncol. 2023, 18, 19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Melia, E.; Fisch, A.-S.; Tinhofer, I.; Parsons, J.L. Targeting Chk1 and Wee1 kinases enhances radiosensitivity of 2D and 3D head and neck cancer models to X-rays and low/high-LET protons. Cell Death Dis. 2025, 16, 128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- da Costa, A.A.B.A.; Chowdhury, D.; Shapiro, G.I.; D’Andrea, A.D.; Konstantinopoulos, P.A. Targeting replication stress in cancer therapy. Nat. Rev. Drug Discov. 2023, 22, 38–58. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Z.; Harish, R.; Elahi, N.; Saini, S.; Telia, A.; Kundlas, M.; Koroleva, A.; Umoh, I.N.; Lota, M.; Bilkhu, M.; et al. Targeting WEE1 Kinase for Breast Cancer Therapeutics: An Update. Int. J. Mol. Sci. 2025, 26, 5701. [Google Scholar] [CrossRef] [Scilit]
- Gong, Y.; Wang, Z.; Zong, W.; Shi, R.; Sun, W.; Wang, S.; Peng, B.; Takeda, S.; Wang, Z.-Q.; Xu, X. PARP1 UFMylation ensures the stability of stalled replication forks. Proc. Natl. Acad. Sci. USA 2024, 121, e2322520121. [Google Scholar] [CrossRef] [Scilit]
- Farmer, H.; McCabe, N.; Lord, C.J.; Tutt, A.N.J.; Johnson, D.A.; Richardson, T.B.; Santarosa, M.; Dillon, K.J.; Hickson, I.; Knights, C.; et al. Targeting the DNA repair defect in BRCA mutant cells as a therapeutic strategy. Nature 2005, 434, 917–921. [Google Scholar] [CrossRef] [Scilit]
- Bryant, H.E.; Schultz, N.; Thomas, H.D.; Parker, K.M.; Flower, D.; Lopez, E.; Kyle, S.; Meuth, M.; Curtin, N.J.; Helleday, T. Specific killing of BRCA2-deficient tumours with inhibitors of poly(ADP-ribose) polymerase. Nature 2005, 434, 913–917. [Google Scholar] [CrossRef] [Scilit]
- Slade, D. PARP and PARG inhibitors in cancer treatment. Genes Dev. 2020, 34, 360–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mao, Y.; Huang, X.; Shuang, Z.; Lin, G.; Wang, J.; Duan, F.; Chen, J.; Li, S. PARP inhibitor olaparib sensitizes cholangiocarcinoma cells to radiation. Cancer Med. 2018, 7, 1285–1296. [Google Scholar] [CrossRef] [Scilit]
- de Haan, R.; van Werkhoven, E.; van den Heuvel, M.M.; Peulen, H.M.U.; Sonke, G.S.; Elkhuizen, P.; van den Brekel, M.W.M.; Tesselaar, M.E.T.; Vens, C.; Schellens, J.H.M.; et al. Study protocols of three parallel phase 1 trials combining radical radiotherapy with the PARP inhibitor olaparib. BMC Cancer 2019, 19, 901. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gupta, N.; Huang, T.-T.; Horibata, S.; Lee, J.-M. Cell cycle checkpoints and beyond: Exploiting the ATR/CHK1/WEE1 pathway for the treatment of PARP inhibitor–resistant cancer. Pharmacol. Res. 2022, 178, 106162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, Y.; Xiao, D.; Li, D.; Peng, M.; Peng, W.; Duan, H.; Yang, X. Combined strategies with PARP inhibitors for the treatment of BRCA wide type cancer. Front. Oncol. 2024, 14, 1441222. [Google Scholar] [CrossRef] [Scilit]
- Oetting, A.; Christiansen, S.; Gatzemeier, F.; Köcher, S.; Bußmann, L.; Böttcher, A.; Stölzel, K.; Hoffmann, A.S.; Struve, N.; Kriegs, M.; et al. Impaired DNA double-strand break repair and effective radiosensitization of HPV-negative HNSCC cell lines through combined inhibition of PARP and Wee1. Clin. Transl. Radiat. Oncol. 2023, 41, 100630. [Google Scholar] [CrossRef] [Scilit]
- Gao, Y.; Zhou, J.; Wang, C.-C.; Wang, Z.-H.; Mao, N.-D.; He, M.-L.; Zhang, P.-P.; Huang, P.; Ye, G.-W.; Zhang, Y.-Q.; et al. Novel ATR/PARP1 Dual Inhibitors Demonstrate Synergistic Antitumor Efficacy in Triple-Negative Breast Cancer Models. Adv. Sci. 2025, 12, e01916. [Google Scholar] [CrossRef] [Scilit]
- Pedersen, L.; Idorn, M.; Olofsson, G.H.; Lauenborg, B.; Nookaew, I.; Hansen, R.H.; Johannesen, H.H.; Becker, J.C.; Pedersen, K.S.; Dethlefsen, C.; et al. Voluntary Running Suppresses Tumor Growth through Epinephrine- and IL-6-Dependent NK Cell Mobilization and Redistribution. Cell Metab. 2016, 23, 554–562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dueva, R.; Krieger, L.M.; Li, F.; Luo, D.; Xiao, H.; Stuschke, M.; Metzen, E.; Iliakis, G. Chemical Inhibition of RPA by HAMNO Alters Cell Cycle Dynamics by Impeding DNA Replication and G2-to-M Transition but Has Little Effect on the Radiation-Induced DNA Damage Response. Int. J. Mol. Sci. 2023, 24, 14941. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feng, Y.; Jiang, Y.; Liu, J.; Liu, J.; Shi, M.; Chen, J.; Zhang, J.; Tian, Y.; Yang, X.; Liu, H. Targeting RPA promotes autophagic flux and the antitumor response to radiation in nasopharyngeal carcinoma. J. Transl. Med. 2023, 21, 738. [Google Scholar] [CrossRef] [Scilit]
- Wong, W.-K.; Guerra Liberal, F.D.C.; McMahon, S.J. DNA Repair Inhibitors Potentiate Fractionated Radiotherapy More Than Single-Dose Radiotherapy in Breast Cancer Cells. Cancers 2022, 14, 3794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, F.-T.; Liu, K.; Garan, L.A.W.; Folly-Kossi, H.; Song, Y.; Lin, S.-J.; Lin, W.-C. A small-molecule inhibitor of TopBP1 exerts anti-MYC activity and synergy with PARP inhibitors. Proc. Natl. Acad. Sci. USA 2023, 120, e2307793120. [Google Scholar] [CrossRef] [Scilit]
- Li, C.; Shen, Q.; Zhang, P.; Wang, T.; Liu, W.; Li, R.; Ma, X.; Zeng, X.; Yin, Y.; Tao, K. Targeting MUS81 promotes the anticancer effect of WEE1 inhibitor and immune checkpoint blocking combination therapy via activating cGAS/STING signaling in gastric cancer cells. J. Exp. Clin. Cancer Res. 2021, 40, 315. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Zou, S.; Zhou, L.; Gao, A.; Xu, J.; He, C.; Zhou, J.; Wu, S.; Chen, Y. RAD18 confers radioresistance of esophagus squamous cell carcinoma through regulating p-DNA-PKcs. Cancer Med. 2022, 11, 3809–3819. [Google Scholar] [CrossRef] [Scilit]
- Lim, J.; Chiou, L.F.; Novy, B.; Chow, E.J.; Norris-Drouin, J.L.; Hardy, P.B.; Popov, K.I.; Vaziri, C.; Bowers, A.A.; Pearce, K. H Development of Next Generation Cell-Permeable Peptide Inhibitors for the Oncological Target MAGE-A4. J. Med. Chem. 2025, 68, 19377–19395. [Google Scholar] [CrossRef] [Scilit]
- Cadzow, L.; Brenneman, J.; Tobin, E.; Sullivan, P.; Nayak, S.; Ali, J.A.; Shenker, S.; Griffith, J.; McGuire, M.; Grasberger, P.; et al. The USP1 Inhibitor KSQ-4279 Overcomes PARP Inhibitor Resistance in Homologous Recombination–Deficient Tumors. Cancer Res. 2024, 84, 3419–3434. [Google Scholar] [CrossRef] [Scilit]
- Torrado, C.; Brenneman, J.; Tobin, E.; Sullivan, P.; Nayak, S.; Ali, J.A.; Shenker, S.; Griffith, J.; McGuire, M.; Grasberger, P.; et al. USP1 inhibition: A journey from target discovery to clinical translation. Pharmacol. Ther. 2025, 271, 108865. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lang, F.; Kaur, K.; Zaheer, J.; Ribeiro, D.L.; Yang, C. Myt1 Kinase: An Emerging Cell-Cycle Regulator for Cancer Therapeutics. Clin. Cancer Res. 2025, 31, 960–964. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ren, L.; Chen, L.; Wu, W.; Garribba, L.; Tian, H.; Liu, Z.; Vogel, I.; Li, C.; Hickson, I.D.; Liu, Y. Potential biomarkers of DNA replication stress in cancer. Oncotarget 2017, 8, 36996–37008. [Google Scholar] [CrossRef] [Scilit]
- Willers, H.; Gheorghiu, L.; Liu, Q.; Efstathiou, J.A.; Wirth, L.J.; Krause, M.; von Neubeck, C. DNA Damage Response Assessments in Human Tumor Samples Provide Functional Biomarkers of Radiosensitivity. Semin. Radiat. Oncol. 2015, 25, 237–250. [Google Scholar] [CrossRef] [Scilit]
- Lukas, C.; Savic, V.; Bekker-Jensen, S.; Doil, C.; Neumann, B.; Sølvhøj Pedersen, R.; Grøfte, M.; Chan, K.L.; Hickson, I.D.; Bartek, J.; et al. 53BP1 nuclear bodies form around DNA lesions generated by mitotic transmission of chromosomes under replication stress. Nat. Cell Biol. 2011, 13, 243–253. [Google Scholar] [CrossRef] [Scilit]
- Stephan, H.; Concannon, C.; Kremmer, E.; Carty, M.P.; Nasheuer, H.-P. Ionizing radiation-dependent and independent phosphorylation of the 32-kDa subunit of replication protein A during mitosis. Nucleic Acids Res. 2009, 37, 6028–6041. [Google Scholar] [CrossRef] [Scilit]
- Schab, A.; Compadre, A.; Drexler, R.; Loeb, M.; Rodriguez, K.; Brill, J.; Harrington, S.; Sandoval, C.; Sanders, B.; Kuroki, L.; et al. Phospho-RPA2 predicts response to platinum and PARP inhibitors in homologous recombination–proficient ovarian cancer. J. Clin. Investig. 2025, 135, e189511. [Google Scholar] [CrossRef] [Scilit]
- Hauge, S.; Eek Mariampillai, A.; Rødland, G.E.; Bay, L.T.E.; Landsverk, H.B.; Syljuåsen, R.G. Expanding roles of cell cycle checkpoint inhibitors in radiation oncology. Int. J. Radiat. Biol. 2023, 99, 941–950. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kciuk, M.; Gruszka, R.; Aleksandrowicz, M.; Śliwińska, A.; Kontek, R. ATR-CHK1 Axis Inhibitors in Gastric Cancer Treatment. Int. J. Mol. Sci. 2025, 26, 7709. [Google Scholar] [CrossRef] [Scilit]
- Buckland, R.J.; Watt, D.L.; Chittoor, B.; Nilsson, A.K.; Kunkel, T.A.; Chabes, A. Increased and Imbalanced dNTP Pools Symmetrically Promote Both Leading and Lagging Strand Replication Infidelity. PLoS Genet. 2014, 10, e1004846. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tarsounas, M.; Sung, P. The antitumorigenic roles of BRCA1–BARD1 in DNA repair and replication. Nat. Rev. Mol. Cell Biol. 2020, 21, 284–299. [Google Scholar] [CrossRef] [Scilit]
- Li, S.; Wang, L.; Wang, Y.; Zhang, C.; Hong, Z.; Han, Z. The synthetic lethality of targeting cell cycle checkpoints and PARPs in cancer treatment. J. Hematol. Oncol. 2022, 15, 147. [Google Scholar] [CrossRef] [Scilit]
- Galan-Cobo, A.; Vokes, N.I.; Qian, Y.; Molkentine, D.; Ramkumar, K.; Paula, A.G.; Pisegna, M.; McGrail, D.J.; Poteete, A.; Cho, S.; et al. KEAP1 and STK11/LKB1 alterations enhance vulnerability to ATR inhibition in KRAS mutant non-small cell lung cancer. Cancer Cell 2025, 43, 1530–1548.e9. [Google Scholar] [CrossRef] [Scilit]
- Mandal, J.; Mandal, P.; Wang, T.-L.; Shih, I.-M. Treating ARID1A mutated cancers by harnessing synthetic lethality and DNA damage response. J. Biomed. Sci. 2022, 29, 71. [Google Scholar] [CrossRef] [Scilit]
- Fukuda, K.; Takeuchi, S.; Arai, S.; Nanjo, S.; Sato, S.; Kotani, H.; Kita, K.; Nishiyama, A.; Sakaguchi, H.; Ohtsubo, K.; et al. Targeting WEE1 enhances the antitumor effect of KRAS-mutated non-small cell lung cancer harboring TP53 mutations. Cell Rep. Med. 2024, 5, 101578. [Google Scholar] [CrossRef] [Scilit]
- Ng, V.; Sinha, S.; Novaj, A.; Ma, J.; McDermott, N.; Pei, X.; Longhini, A.L.F.; Grimsley, H.; Gardner, R.; Rosen, E.; et al. Genotype-Directed Synthetic Cytotoxicity of ATR Inhibition with Radiotherapy. Clin. Cancer Res. 2024, 30, 5643–5656. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Min, A.; Im, S.-A.; Jang, H.; Kim, S.; Lee, M.; Kim, D.K.; Yang, Y.; Kim, H.-J.; Lee, K.-H.; Kim, J.W.; et al. AZD6738, A Novel Oral Inhibitor of ATR, Induces Synthetic Lethality with ATM Deficiency in Gastric Cancer Cells. Mol. Cancer Ther. 2017, 16, 566–577. [Google Scholar] [CrossRef] [Scilit]
- Zhang, A.; Miao, K.; Sun, H.; Deng, C.X. Tumor heterogeneity reshapes the tumor microenvironment to influence drug resistance. Int. J. Biol. Sci. 2022, 18, 3019–3033. [Google Scholar] [CrossRef] [Scilit]
- Rouault, C.D.; Charafe-Jauffret, E.; Ginestier, C. The interplay of DNA damage, epigenetics and tumour heterogeneity in driving cancer cell fitness. Nat. Commun. 2025, 16, 8733. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martorana, F.; Da Silva, L.A.; Sessa, C.; Colombo, I. Everything Comes with a Price: The Toxicity Profile of DNA-Damage Response Targeting Agents. Cancers 2022, 14, 953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Drew, Y.; Zenke, F.T.; Curtin, N.J. DNA damage response inhibitors in cancer therapy: Lessons from the past, current status and future implications. Nat. Rev. Drug Discov. 2025, 24, 19–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, H.; Tian, Y.; Chen, H.; Qian, Y.; Li, J.; Niu, D.; Zhao, W.; Wu, Y.; Zhang, X.; Tang, T.; et al. Targeting DNA damage response pathways in tumor drug resistance: Mechanisms, clinical implications, and future directions. Drug Resist. Updates 2025, 83, 101287. [Google Scholar] [CrossRef] [Scilit]
- Gkikoudi, A.; Kalospyros, S.A.; Triantopoulou, S.; Logotheti, S.; Softa, V.; Kappas, C.; Theodorou, K.; Laiakis, E.C.; Manda, G.; Terzoudi, G.I.; et al. Molecular Biomarkers for Predicting Cancer Patient Radiosensitivity and Radiotoxicity in Clinical Practice. Appl. Sci. 2023, 13, 12564. [Google Scholar] [CrossRef] [Scilit]
- Baxter, J.S.; Zatreanu, D.; Pettitt, S.J.; Lord, C.J. Resistance to DNA repair inhibitors in cancer. Mol. Oncol. 2022, 16, 3811–3827. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.; Xu, H.; George, E.; Hallberg, D.; Kumar, S.; Jagannathan, V.; Medvedev, S.; Kinose, Y.; Devins, K.; Verma, P.; et al. Combining PARP with ATR inhibition overcomes PARP inhibitor and platinum resistance in ovarian cancer models. Nat. Commun. 2020, 11, 3726. [Google Scholar] [CrossRef] [Scilit]
- Zou, Y.; Zhang, H.; Chen, P.; Tang, J.; Yang, S.; Nicot, C.; Guan, Z.; Li, X.; Tang, H. Clinical approaches to overcome PARP inhibitor resistance. Mol. Cancer 2025, 24, 156. [Google Scholar] [CrossRef] [Scilit]
- O’Leary, P.C.; Chen, H.; Doruk, Y.U.; Williamson, T.; Polacco, B.; McNeal, A.S.; Shenoy, T.; Kale, N.; Carnevale, J.; Stevenson, E.; et al. Resistance to ATR Inhibitors Is Mediated by Loss of the Nonsense-Mediated Decay Factor UPF2. Cancer Res. 2022, 82, 3950–3961. [Google Scholar] [CrossRef] [Scilit]
- Zhao, X.; Kim, I.-K.; Kallakury, B.; Chahine, J.J.; Iwama, E.; Pierobon, M.; Petricoin, E.; McCutcheon, J.N.; Zhang, Y.-W.; Umemura, S.; et al. Acquired small cell lung cancer resistance to Chk1 inhibitors involves Wee1 up-regulation. Mol. Oncol. 2021, 15, 1130–1145. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Murray, C.E.; Kornepati, A.V.R.; Ontiveros, C.; Liao, Y.; de la Peña Avalos, B.; Rogers, C.M.; Liu, Z.; Deng, Y.; Bai, H.; Kari, S.; et al. Tumour-intrinsic PDL1 signals regulate the Chk2 DNA damage response in cancer cells and mediate resistance to Chk1 inhibitors. Mol. Cancer 2024, 23, 242. [Google Scholar] [CrossRef] [Scilit]
- Fitsiou, E.; Soto-Gamez, A.; Demaria, M. Biological functions of therapy-induced senescence in cancer. Semin. Cancer Biol. 2022, 81, 5–13. [Google Scholar] [CrossRef] [Scilit]
- Ghorai, A.; Singh, B.; Dutt, S. Biphasic DNA damage and non-canonical replication stress response govern radiation-induced senescence in glioblastoma. J. Cell Sci. 2024, 137, jcs261844. [Google Scholar] [CrossRef] [Scilit]
- Softah, A.; Alotaibi, M.R.; Alhoshani, A.R.; Saleh, T.; Alhazzani, K.; Almutairi, M.M.; AlRowis, R.; Alshehri, S.; Albekairy, N.A.; Harada, H.; et al. The Combination of Radiation with PARP Inhibition Enhances Senescence and Sensitivity to the Senolytic, Navitoclax, in Triple Negative Breast Tumor Cells. Biomedicines 2023, 11, 3066. [Google Scholar] [CrossRef] [Scilit]
- Kwon, J.; Bakhoum, S.F. The Cytosolic DNA-Sensing cGAS–STING Pathway in Cancer. Cancer Discov. 2020, 10, 26–39. [Google Scholar] [CrossRef] [Scilit]
- Pateras, I.S.; Havaki, S.; Nikitopoulou, X.; Vougas, K.; Townsend, P.A.; Panayiotidis, M.I.; Georgakilas, A.G.; Gorgoulis, V.G. The DNA damage response and immune signaling alliance: Is it good or bad? Nature decides when and where. Pharmacol. Ther. 2015, 154, 36–56. [Google Scholar] [CrossRef] [Scilit]
- Huang, Z.; Zhu, J.; Zhou, Y.L.; Shi, J. The cGAS-STING pathway: A dual regulator of immune response in cancer and therapeutic implications. J. Transl. Med. 2025, 23, 766. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, R.; Wu, Y.; Shen, F.; Chen, S.; Yang, X.; Lin, Y.; Fang, Y.; Shen, J. Manganese-coordinated nanoparticles loaded with CHK1 inhibitor dually activate cGAS-STING pathway and enhance efficacy of immune checkpoint therapy. Biomaterials 2025, 319, 123199. [Google Scholar] [CrossRef] [Scilit]
- Sakellaropoulos, T.; Vougas, K.; Narang, S.; Koinis, F.; Kotsinas, A.; Polyzos, A.; Moss, T.J.; Piha-Paul, S.; Zhou, H.; Kardala, E.; et al. A Deep Learning Framework for Predicting Response to Therapy in Cancer. Cell Rep. 2019, 29, 3367–3373.e4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badwan, B.A.; Liaropoulos, G.; Kyrodimos, E.; Skaltsas, D.; Tsirigos, A.; Gorgoulis, V.G. Machine learning approaches to predict drug efficacy and toxicity in oncology. Cell Rep. Methods 2023, 3, 100413. [Google Scholar] [CrossRef] [Scilit] [PubMed]
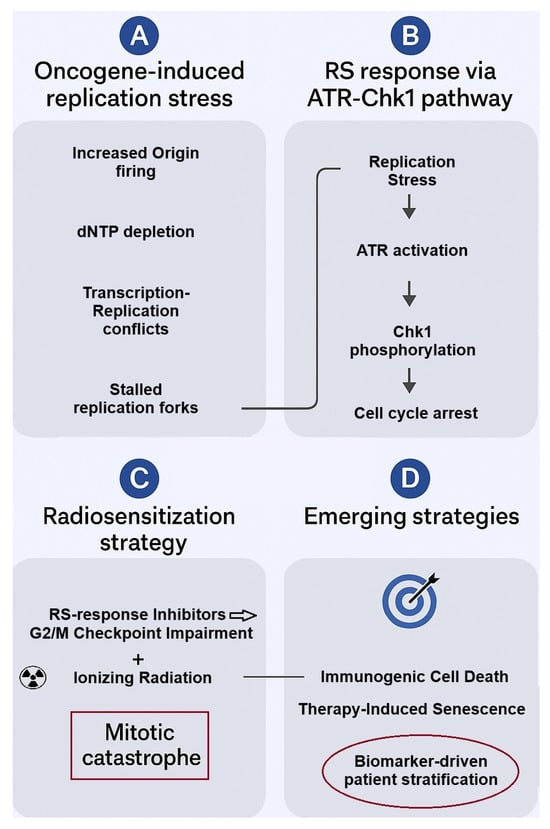
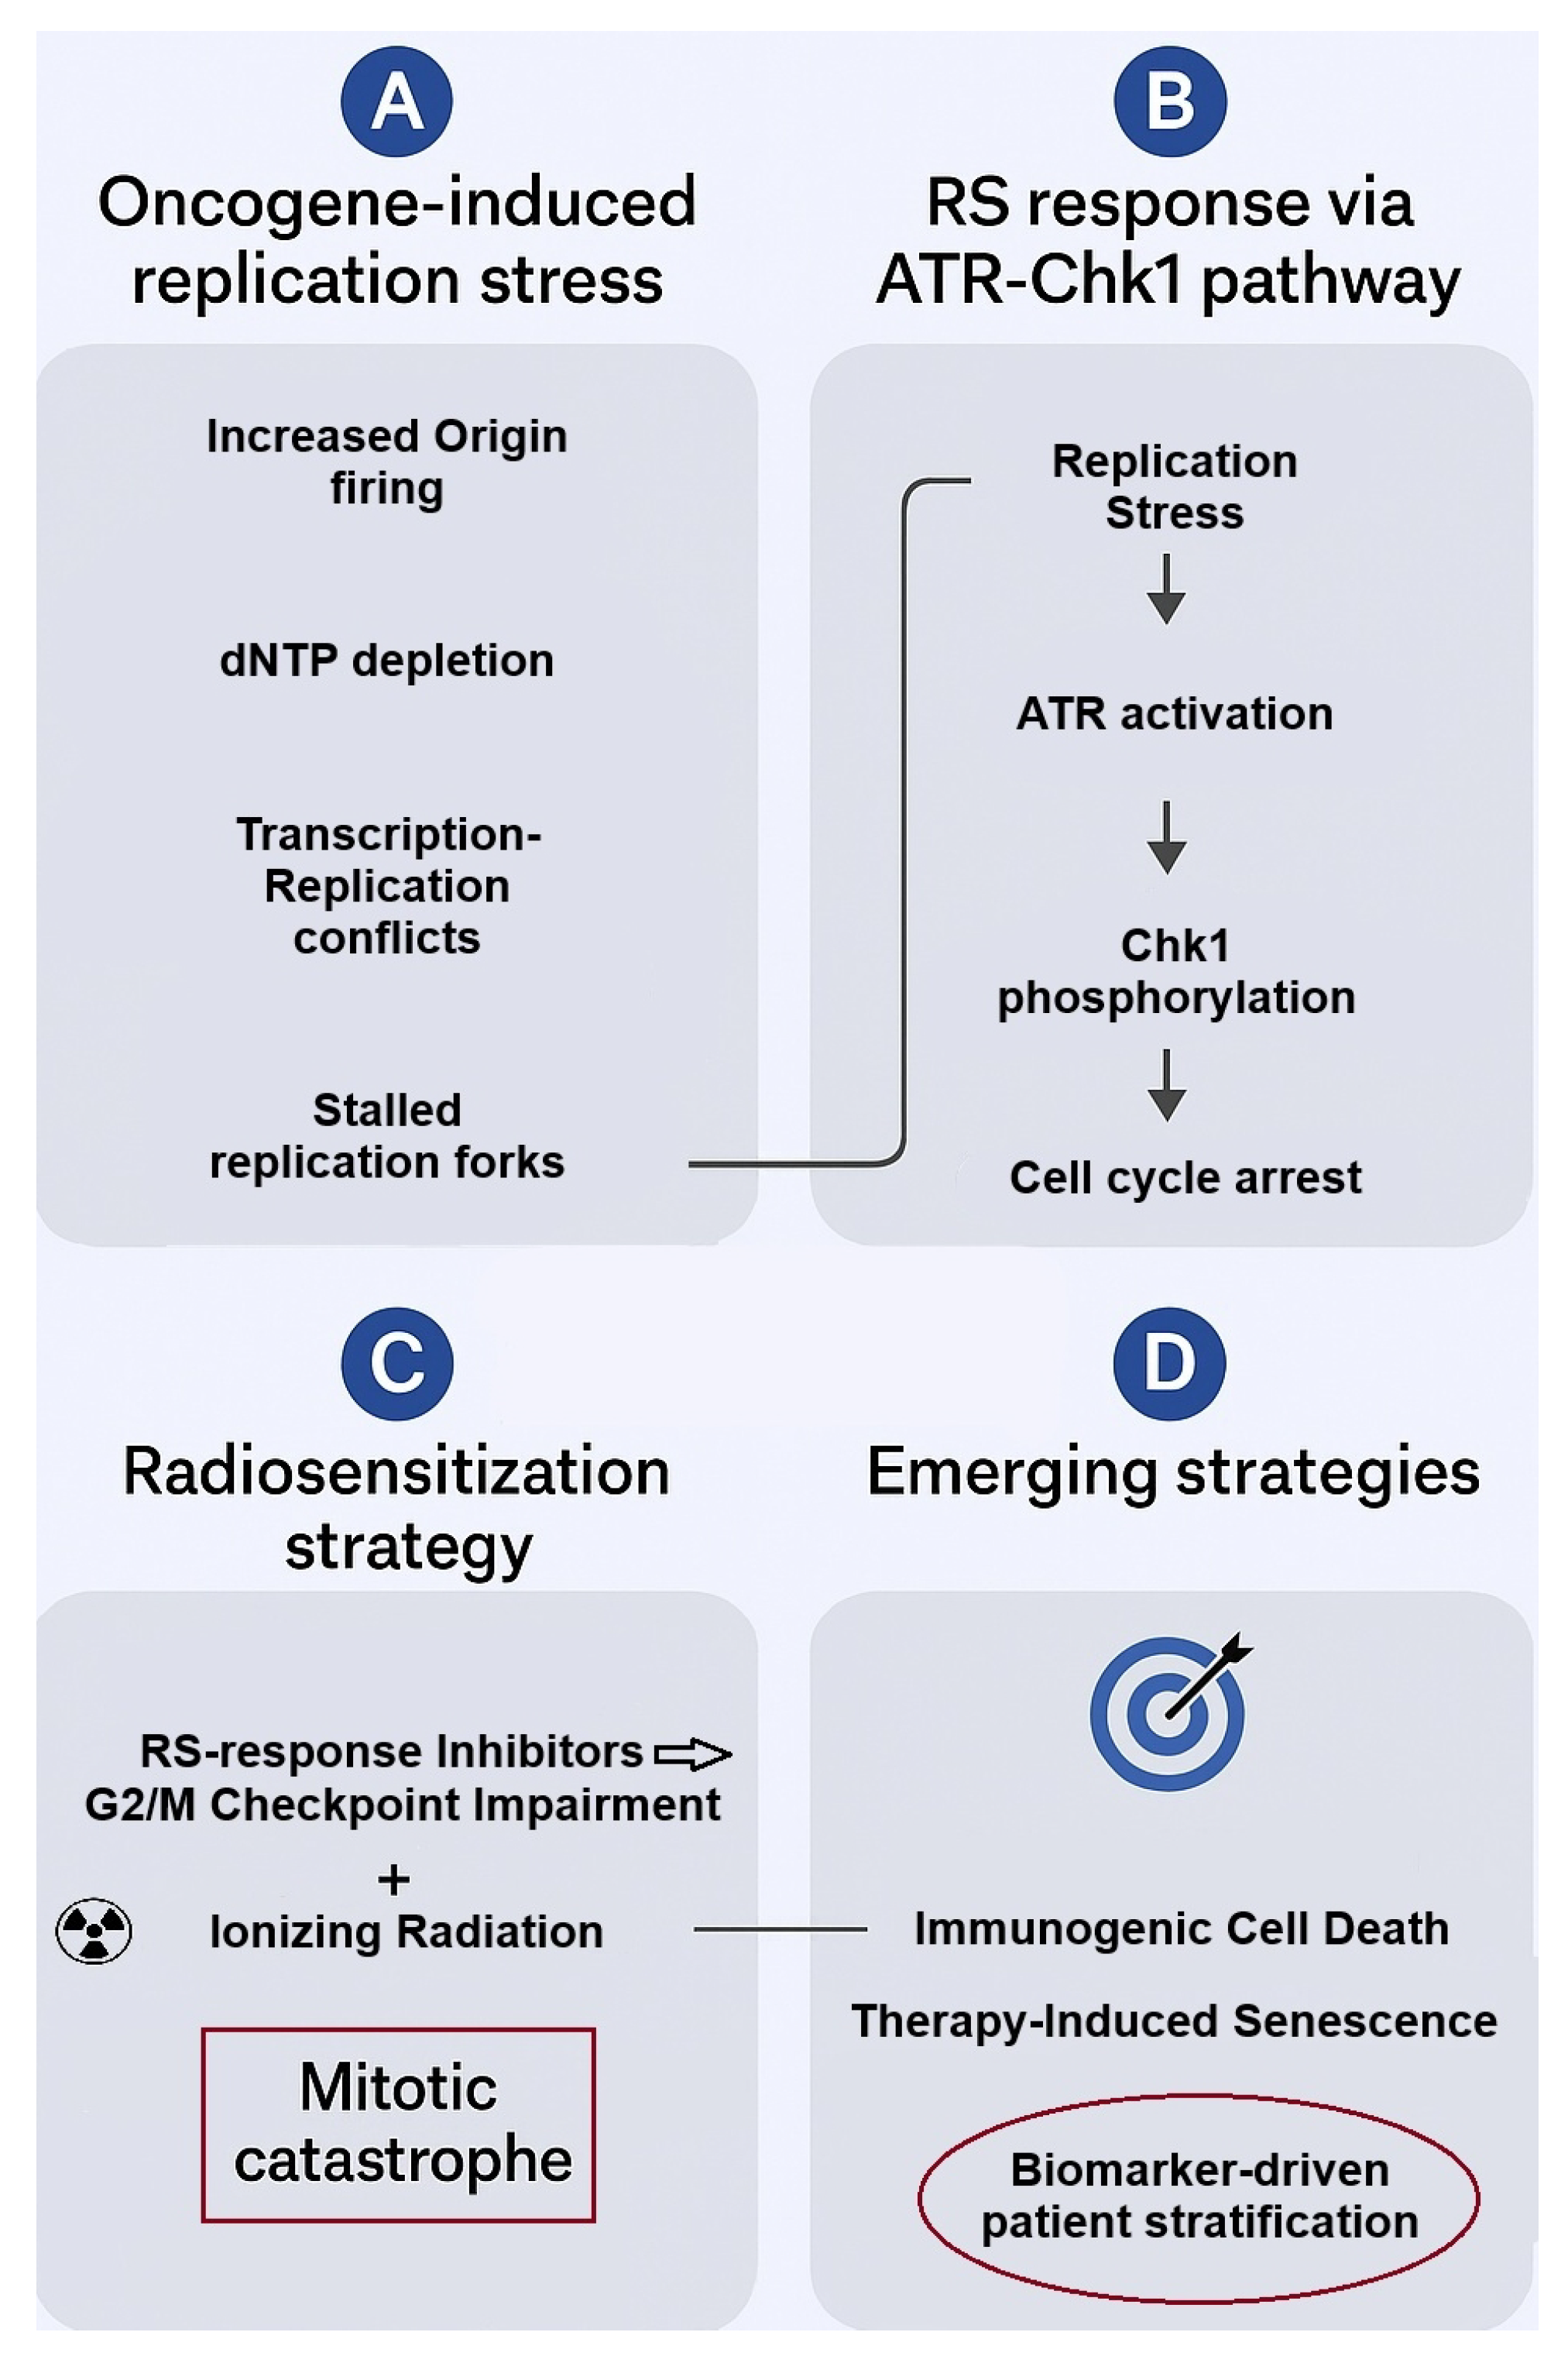

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.