


Abstract
This review presents an innovative and timely exploration of how cytoprotection can serve as a cohesive therapeutic approach by which to address the hemorrhage–thrombosis paradox. Presenting counteraction of both hemorrhage and thrombosis as phase-dependent outcomes of vascular dysregulation, the manuscript synthesizes conceptual, experimental, and clinical evidence into a unified systems-level model focused on the stable gastric pentadecapeptide BPC 157, which acts as a cytoprotective mediator. In rodents, BPC 157 can simultaneously counteract hemorrhage and thrombosis without directly affecting the coagulation cascade (aggregometry, thromboelastometry). This cytoprotective framework (decreased hemorrhage, decreased thrombosis) stands with presentation of both hemorrhage and thrombosis in the wound, arrhythmias, and Virchow triad, and resolution of these disturbances. As proof of the concept (full cytoprotective effect), a vasoprotective cytoprotective mediator capable of bidirectional regulation, BPC 157, is effective for wound healing, arrhythmia control, and normalization of Virchow’s triad (i.e., following major injuries, occlusion/occlusion-like syndromes). As a comparison from a cytoprotective (partial vs. full) standpoint, conventional agents—anticoagulants, antiplatelet drugs, and fibrinolytics—provide only partial protection by targeting isolated components of hemostasis. Beta blockers, calcium channel blockers, prostaglandins, NO modulators, ACE inhibitors, and statins each exert broader cytoprotective effects; however, these actions remain incomplete and context-dependent, typically unidirectional, dose-limited, or are achieved at the expense of opposing pathological risks. Contrarily, for BPC 157, decreased hemorrhage (including both anticoagulants and antiplatelet agents), decreased thrombosis, effective wound healing, arrhythmia control, and normalization of Virchow’s triad involve preservation of endothelial integrity, normalization of microcirculation, modulation of the NO system, stabilization of hemostatic balance, and recruitment of adaptive collateral pathways. Nevertheless, reliance on preclinical models necessitates further clinical validation.
1. Introduction
This review attempts to present an innovative and timely exploration of how cytoprotection [1,2,3,4,5,6,7,8,9] can serve as a cohesive therapeutic approach to tackle the hemorrhage–thrombosis paradox [10,11,12,13,14,15]. Presenting counteraction of both hemorrhage and thrombosis as phase-dependent outcomes of vascular dysregulation, the manuscript synthesizes conceptual, experimental, and clinical evidence into a unified systems-level model focused on the stable gastric pentadecapeptide BPC 157, which acts as a cytoprotective mediator [16,17,18,19,20,21,22,23,24,25,26]. In rodents, BPC 157 can simultaneously counteract hemorrhage and thrombosis without directly affecting the coagulation cascade (aggregometry, thromboelastometry) [16,17,18,19,20,21,22,23,24,25,26].
We advocate that the cytoprotection concept, as a process to preserve and reestablish homeostasis [1,2,3,4,5,6,7,8,9], challenges the classical view of hemostasis and thrombosis as opposing pathological states [10,11,12]. Within this conventional framework, anticoagulants prevent thrombosis but induce bleeding, whereas procoagulants control bleeding while promoting thrombosis [13]. In contrast, the cytoprotection concept of vascular integrity frames both hemostasis and thrombosis as processes with an essential dual capacity to preserve tissue integrity and restore homeostasis, irrespective of the nature of the injury. Accordingly, in bleeding/thrombosis disorders, true cytoprotection is the bidirectional normalization of vascular and cellular homeostasis, counteracting both hemorrhage and thrombosis without inducing opposite-pathology toxicity. Importantly, as a universal reversal strategy, this approach would transcend the heterogeneity of anticoagulants and the involvement of distinct coagulation pathways. At present, unlike specific antagonists, no single agent is applicable to counteract both heparin- and warfarin-induced bleeding [14,15], a common antidote is lacking.
Translating this concept into practice through the application of a cytoprotective agent (i.e., the stable gastric pentadecapeptide BPC 157 [16,17,18,19,20,21,22,23,24,25,26]) may be important. This implies that a true cytoprotective therapy should normalize pathological bleeding or thrombosis in either direction without provoking opposing toxicity [16,17,18,19,20,21,22,23,24,25,26]. Such coordinated and balanced control of bleeding and thrombosis raises the longstanding question of an “ideal agent” capable of preserving therapeutic efficacy while avoiding adverse effects.
From a cytoprotective viewpoint—where agents may share partial cytoprotective properties (e.g., antioxidative, gastroprotective, cardioprotective, or organ-protective effects)—partial solutions have been achieved with conventional anticoagulants, antiplatelet agents, and fibrinolytics [10,11,12,13,14,15]. Ultimately, however, given that the cytoprotection concept (cell protection) was born in the stomach [1,2,3,4,5,6,7,8,9], the stable gastric pentadecapeptide BPC 157 has emerged as a particularly relevant cytoprotective therapy [16,17,18,19,20,21,22,23,24,25,26]. This study also includes other agents exhibiting cytoprotective properties, including prostaglandin analogues [1,2,3,4,5,6,7,8,9], antioxidants [27,28,29], angiotensin-converting enzyme inhibitors [30], statins [31,32], beta blockers [33,34], and calcium channel blockers [35,36]. These illustrate that cytoprotection is not a distinct pharmacological class but rather a shared therapeutic property across diverse drug groups. Peptides such as PDGF-BB [37], TGF-β1 [38], FGF-2/bFGF [39], VEGF [40], IGF-1 [41], and BMPs [42] were not incorporated into this framework. Thus, cytoprotection currently represents a conceptual therapeutic effect rather than a standardized clinical drug category.
Stable Gastric Pentadecapeptide BPC 157
Among cytoprotective agents, BPC 157 has accumulated the most extensive preclinical evidence [16,17,18,19,20,21,22,23,24,25,26]. Unlike other compounds, it is native and stable in human gastric juice for more than 24 h and has been proposed as a mediator of cytoprotection capable of transmitting gastrointestinal mucosal integrity to systemic organ protection [16,17,18,19,20,21,22,23,24,25,26]. This distinctive property underlies its pleiotropic beneficial effects. This includes efficacy via multiple routes, including oral administration. These effects are attributed to its modulatory interactions with multiple molecular pathways [43,44,45,46,47,48,49,50,51,52,53,54], particularly the nitric oxide (NO) system [16,55,56,57]. Toxicological studies have demonstrated an exceptionally favorable safety profile, with no lethal dose achieved (LD1 not reached) even at doses of 2 g/kg i.v. or i.g. in mice [16,17,18,19,20,21,22,23,24,25,26]. Human data remain limited but encouraging. BPC 157 was found to be effective and well tolerated in phase II clinical trials in ulcerative colitis and subsequently in small clinical studies addressing knee pain and interstitial cystitis, all without reported adverse effects [58,59,60,61]. These findings are supported by toxicological evaluations [62,63] and patient reports [64,65,66], consistent with previous assessments [16].
In hemorrhage- and thrombosis-focused experimental studies, bleeding and thrombosis were treated as specific cytoprotection targets [16,17,18,19,20,21,22,23,24,25,26], incorporating decreased hemorrhage and decreased thrombosis as part of a cytoprotection framework. The first direct evidence of BPC 157’s antithrombotic action was demonstrated in a rat abdominal aorta anastomosis model, where it counteracted thrombosis formation and reversed established clots [67]. Its capacity to normalize prolonged bleeding was subsequently shown in models involving heparin, warfarin, aspirin, and traumatic injury [68,69]. Aggregometry and thromboelastometry studies further indicated that BPC 157 restores platelet function without affecting coagulation pathways [70].
Additional evidence (decreased hemorrhage, decreased thrombosis) derives from severe models characterized by the coexistence of organ hemorrhage and widespread thrombosis, including thrombohemorrhagic disorders, major vessel occlusion, occlusion-like syndromes, and multiorgan failure [71,72,73,74,75,76,77]. These conditions were found to be induced by vascular occlusion, noxious procedures [78,79,80,81], or toxic agents [82,83,84,85,86,87], and were consistently reversed by BPC 157 therapy. A distinctive rescue mechanism involves the rapid activation of collateral circulation, particularly via the azygos vein, leading to restoration of systemic hemodynamics. Importantly, BPC 157 exhibits a modulatory interaction with the NO system, counteracting both NO inhibition and NO overactivity [16], and consistently antagonizes the adverse vascular effects of non-steroidal anti-inflammatory drugs [88].
2. Cytoprotection, Anticoagulants, Antiplatelet Agents, and Fibrinolytics
2.1. Anticoagulants and Cytoprotection: Direct Oral Anticoagulants (DOACs), Unfractionated Heparin, and Low-Molecular-Weight Heparins (LMWHs)
Many anticoagulants exhibit cytoprotective or pleiotropic effects beyond anticoagulation, including endothelial stabilization, anti-inflammatory activity, and modulation of oxidative, fibrotic, and cellular injury pathways [89,90,91,92,93,94]. Although not always described as “cytoprotection,” these actions align with the concept of preserving cellular integrity [1,2,3,4,5,6,7,8,9].
DOACs (dabigatran, rivaroxaban, apixaban, edoxaban) confer endothelial protection, reduce inflammation, prevent oxidative damage, limit fibrosis, and preserve tissue integrity via PAR signaling pathways [89,90,91]. Clinical evidence suggests that oral anticoagulants can lower inflammatory biomarkers, consistent with non-hemostatic cytoprotective effects [90]. DOACs preserve tight junction proteins and reduce endothelial permeability in vitro, further supporting their protective role [91].
LMWHs (e.g., enoxaparin) inhibit complement activation and neutrophil elastase, protecting cells in extracorporeal circulation models [92]. Factor Xa inhibition modulates PAR signaling on endothelial and immune cells, mitigating inflammation [93]. Heparin additionally protects the endothelial glycocalyx and mediates anti-inflammatory interactions independently of antithrombin, contributing to vascular protection [94].
2.2. Warfarin and Cytoprotection
Warfarin, in contrast, lacks cytoprotective effects and may promote vascular dysfunction [95,96,97,98,99,100,101]. By inhibiting vitamin K-dependent matrix Gla protein, warfarin accelerates arterial and valvular calcification, increases susceptibility to oxidative stress, and impairs endothelial survival [95,96,97,98,99]. Consequently, warfarin therapy reduces the vasculature’s intrinsic cytoprotective potential [100,101].
2.3. Antiplatelet Agents and Cytoprotection
Aspirin and P2Y12 inhibitors (clopidogrel, ticagrelor) provide antithrombotic effects along with endothelial protection, anti-inflammatory activity, and reduction of oxidative stress [102,103,104,105,106,107]. Aspirin plays a mechanistic role in foundational gastric cytoprotection studies, demonstrating prostaglandin-mediated adaptive defense via cyclooxygenase inhibition [1,3].
2.4. Fibrinolytics and Indirect Cytoprotection
Fibrinolytic agents (tPA, streptokinase, urokinase) primarily dissolve thrombi but can indirectly protect tissues by restoring perfusion and limiting ischemic injury, apoptosis, oxidative stress, and secondary inflammation [108,109,110,111,112]. In myocardial and cerebral ischemia, fibrinolysis reduces infarct size and tissue damage, although cytoprotection is secondary to thrombus removal [112].
2.5. Hemorrhage and Thrombosis: Anticoagulant Cytoprotection
Despite their preventive intent, anticoagulants can paradoxically induce thrombosis under certain conditions. Examples include heparin-induced thrombocytopenia (HIT), where antibodies against the heparin–PF4 complex cause massive platelet activation [113], and warfarin-induced skin necrosis from transient hypercoagulability due to protein C/S depletion [114,115]. DOACs may trigger thrombosis in cases of underdosing (e.g., renal impairment), and abrupt anticoagulant withdrawal can produce rebound hypercoagulability [116].
Even with low-risk alternatives (LMWHs, fondaparinux, heparinoids), residual HIT risk persists [117,118,119]. Warfarin initiation often requires bridging with UFH or LMWH to mitigate early hypercoagulability [120,121]. Emergency reversal agents (protamine for heparin and idarucizumab for dabigatran), which lack intrinsic prothrombotic properties, rapidly restore hemostasis but may be associated with thrombotic events [122,123,124,125,126]. These events are most plausibly attributable to abrupt neutralization of anticoagulation and re-exposure of the patient’s underlying prothrombotic state rather than to the direct procoagulant effects of the reversal agents.
2.6. Hemorrhage and Thrombosis: Antiplatelet Cytoprotection
Antiplatelet agents, though designed to prevent thrombosis, can also cause rare paradoxical events, including thrombocytopenia-induced thrombosis (e.g., GPIIb/IIIa inhibitors, thienopyridines) [127,128,129] and rebound platelet hyperreactivity after abrupt cessation, especially around percutaneous coronary interventions [130]. Temporary discontinuation of low-dose aspirin for surgery may increase cardiovascular morbidity and mortality [131].
2.7. Hemorrhage and Thrombosis: Fibrinolytic Cytoprotection
Fibrinolytics can paradoxically induce thrombotic events despite their clot-dissolving activity. Rapid clot lysis exposes procoagulant surfaces, activates platelets, thrombin, and coagulation factors, and may precipitate reocclusion or recurrent thrombosis, termed the “thrombolytic paradox” [132,133,134,135,136]. Plasmin generated during fibrinolysis can additionally activate platelets or endothelial cells under inflammatory conditions, temporarily increasing thrombotic risk [136].
These points are summarized in Table 1.
Table 1.
Summary including anticoagulants, antiplatelets, fibrinolytics, and BPC 157, highlighting their effects on thrombosis and bleeding and how they “tip the hemostatic balance”.
2.8. Thrombohemorrhagic Disorders: A Hemostatic Paradox of Simultaneous Thrombosis and Hemorrhage
Thrombohemorrhagic disorders, in which thrombosis and bleeding occur concurrently, reflect profound dysregulation of vascular and cellular homeostasis rather than simple deficiencies or excesses of clotting factors. Conceptually, this represents a failure of cytoprotective mechanisms that normally preserve endothelial integrity and maintain hemostatic balance. Conventional therapies have not systematically leveraged cytoprotection to address these syndromes.
Disseminated intravascular coagulation (DIC) exemplifies this paradox: uncontrolled thrombin generation causes microvascular thrombosis, while consumption of platelets and clotting factors produces bleeding. Triggers include sepsis, trauma, malignancy, and obstetric complications, involving excessive procoagulant activation, impaired anticoagulant pathways, endothelial injury, and variable fibrinolysis. Therapy focuses on treating the underlying cause, which is most effective in restoring hemostasis [137]. Supportive interventions—platelets, fresh frozen plasma, cryoprecipitate—address critical deficiencies but do not prevent ongoing microthrombosis. Low-dose heparin may be considered when thrombosis predominates, but bleeding risk must be carefully weighed [138].
Thrombotic microangiopathies (TMAs), such as thrombotic thrombocytopenic purpura (TTP) and atypical hemolytic uremic syndrome (aHUS), similarly demonstrate this dual risk. Widespread microvascular platelet-rich thrombi cause thrombocytopenia, hemolytic anemia, and organ ischemia while predisposing to bleeding. Plasma exchange in TTP removes ultra-large von Willebrand factor multimers and pathogenic autoantibodies, reducing thrombosis and mortality [139]. Complement inhibition with eculizumab in aHUS prevents microthrombus formation and preserves hematologic and renal function [140,141]. Platelet transfusions are generally reserved for life-threatening hemorrhage.
Effective management requires early recognition and mechanism-directed therapy, as supportive measures alone are insufficient. Interventions—anticoagulation, plasma exchange, complement inhibition—must be tailored to dominant pathophysiology, continuously balancing thrombosis and hemorrhage, guided by close laboratory monitoring.
These syndromes illustrate a fundamental limitation of conventional anticoagulants, antiplatelets, and fibrinolytics: by acting on discrete hemostatic components, they inevitably exchange thrombotic risk for bleeding risk or vice versa. This paradox highlights the absence of a true cytoprotective mechanism capable of preserving endothelial integrity, maintaining cellular homeostasis, and restoring physiologic hemostasis.
Agents such as BPC 157, with demonstrated pleiotropic cytoprotective effects, may offer a therapeutic approach that directly addresses this hemostatic paradox by simultaneously supporting vascular and cellular homeostasis while counteracting both thrombosis and hemorrhage.
2.9. BPC 157 Cytoprotection
Conceptual theory implementation (decreased hemorrhage, decreased thrombosis) holds the cytoprotection concept [1,2,3,4,5,6,7,8,9], though it is not organ specific (although formed in the stomach). A systemic protection (cytoprotection → organoprotection, i.e., gastrointestinal tract maintenance transmitted to other organs therapy) is achieved by administering cytoprotective agents and via the innate pleiotropic beneficial effects attributed to those agents [1,2,3,4,5,6,7,8,9]. This principle is much more attributable to BPC 157 than to other cytoprotection agents mentioned before [16,17,18,19,20,21,22,23,24,25,26].
There, the stable gastric pentadecapeptide BPC 157, holds particular cardioprotection, anti-thrombotic, anti-hemorrhagic, anti-arrhythmic, and vascular recovery potential, particularly during ischemia/reperfusion injury recovery [16,17,18,19,20,21,22,23,24,25,26]. Specifically, principle verification (decreased hemorrhage, decreased thrombosis) includes a complex experimental model range [16,17,18,19,20,21,22,23,24,25,26] that encompasses vessel anastomosis [67], tail or leg amputation, anticoagulants, antiplatelets [68,69], organ perforation [81,142], vessel occlusion [71,72,73,74,75,76], severe injury induction [78,79,80,81], agent application [82,83,84,85,86,87], and occlusion/occlusion-like syndrome. Also included are counteractions of those aggravated by NO/NO synthase (NOS) blockade (L-NAME) or NO overactivity (L-arginine) [69,85]. Notably, as pointed out, this range also includes the simultaneous presentation of organ hemorrhage and thrombosis and counteraction. Additional evidence that BPC 157 may rescue thrombocyte function without affecting coagulation pathways [68,69] includes aggregometry and thromboelastometry studies [70]. Notably, BPC 157 may recover prostaglandin function, given the counteraction of NSAID-induced adverse effects [88].
2.10. Verification of the Cytoprotective Effects (Decreased Hemorrhage, Decreased Thrombosis) Through Three Confirmatory Principles: (i) Wound, (ii) Arrhythmias, and (iii) Virchow Triad
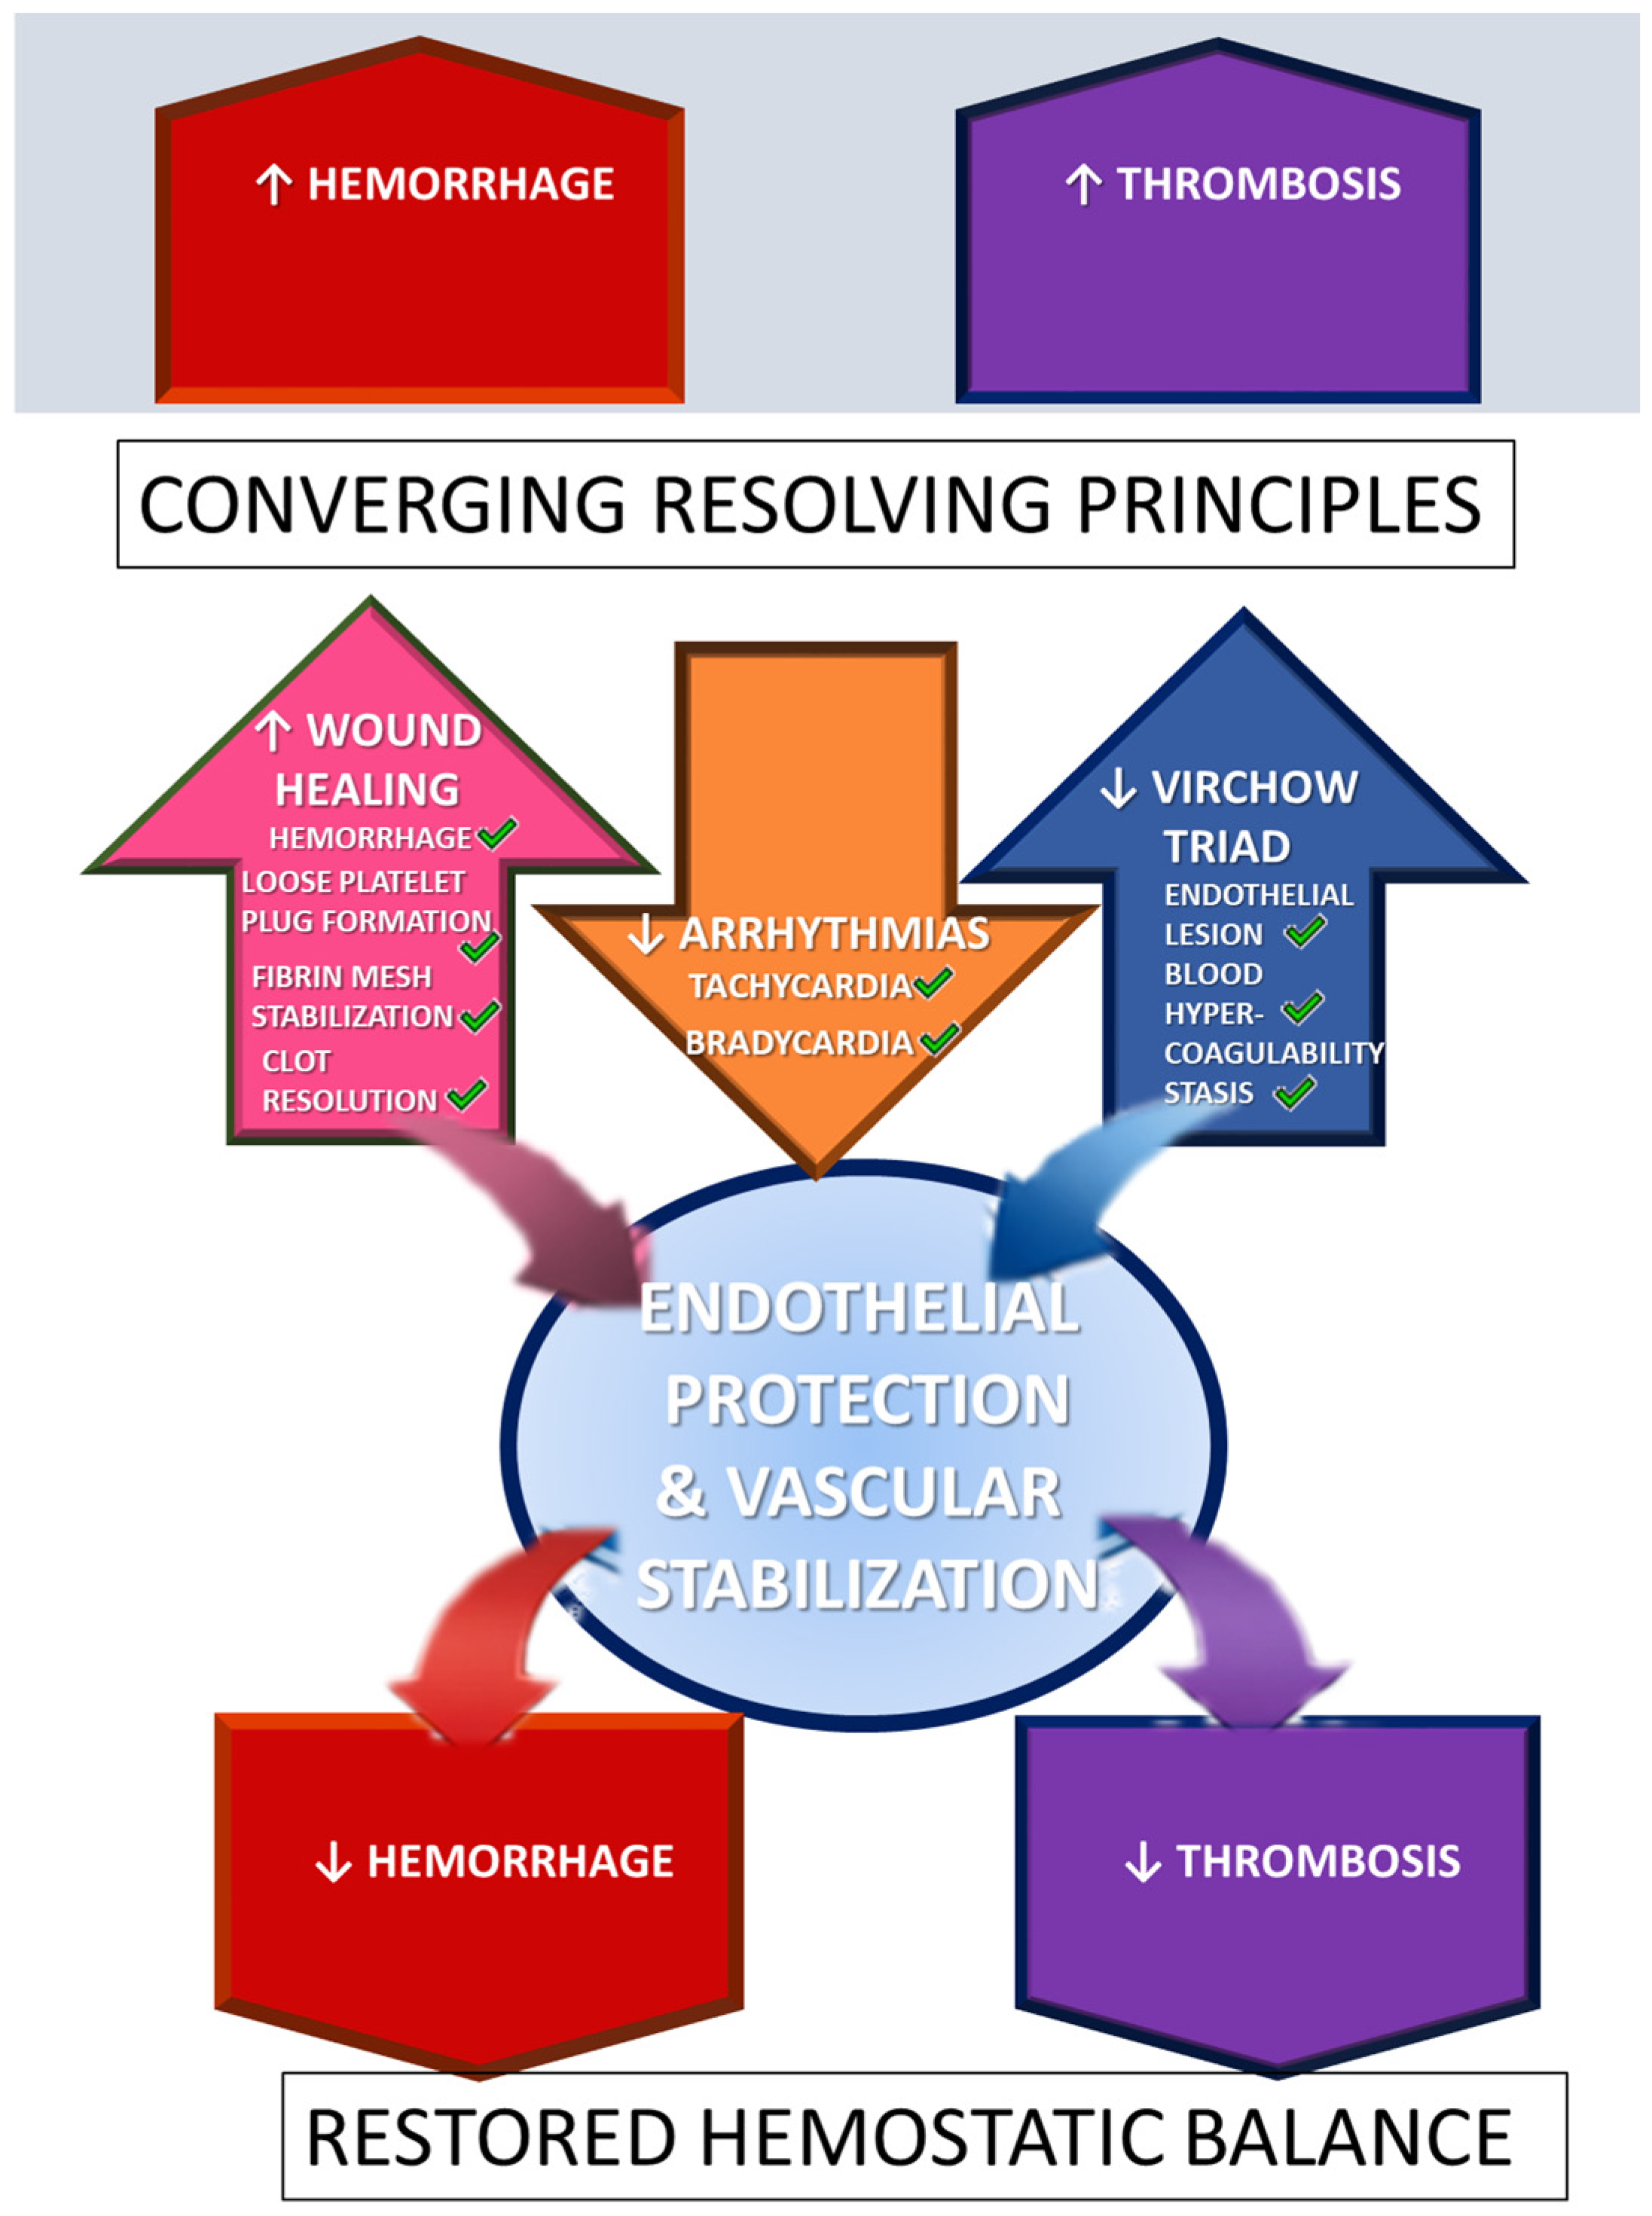
These cytoprotective effects, decreased hemorrhage and decreased thrombosis, conceptually anchor three confirmatory principles that provide presentation of both hemorrhage and thrombosis—(i) wound, (ii) arrhythmias, and (iii) Virchow triad. These (decreased hemorrhage, decreased thrombosis) have to be reversed in order to achieve (i) wound healing, (ii) arrhythmia mitigation, and (iii) normalization of Virchow’s triad (see Figure 1). BPC 157 therapy full accomplishes all of these points [16,17,18,19,20,21,22,23,24,25,26], which is significant given that both hemorrhage and thrombosis regularly need to be counteracted simultaneously.
Wound healing, in particular, encompasses all four major hemostatic events—vascular constriction, loose platelet plug formation, fibrin mesh stabilization, and clot resolution—which occur in a coordinated sequence after vascular injury [143,144,145]. Accordingly, in hemorrhage/thrombosis terms, the principle ↑ wound healing = ↓ hemorrhage and ↓ thrombosis applies, as agents that promote wound healing, such as BPC 157, effectively reduce both bleeding and thrombotic risk. Taken as a conceptual model, these confirmatory endpoints also provide a framework for evaluating other cytoprotective agents, although none matches the comprehensive systemic efficacy of BPC 157.
Figure 1.
Converging resolving principles. Considering that hemorrhage and thrombosis are both involved in the wound, arrhythmia, and Virchow triad, the effects on the circumstances of wound healing, arrhythmia, and Virchow triad were considered as key proof of the agent’s counteracting activity (green tick marks) on either hemorrhage or thrombosis, or counteraction of both hemorrhage and thrombosis [16,17,18,19,20,21,22,23,24,25,26,145].
3. Wound Healing
3.1. BPC 157: Wound Healing as a Resolving Principle for Hemorrhage/Thrombosis Therapy
Wound healing has long been recognized as an inherent component of the cytoprotection concept and a central mediator of cytoprotective agent activity [1,2,3,4,5,6,7,8,9,16,17,18,19,20,21,22,23,24,25,26]. In the context of BPC 157 therapy, wound healing provides a unifying framework for resolving the apparent paradox of simultaneously counteracting hemorrhage and thrombosis [145]. This can be particularly seen given the comparative studies reviewed [145]. As a conceptual principle, we have proposed that any agent truly promoting wound healing must, by necessity, normalize both bleeding and thrombosis, depending on the phase of vascular repair [68].
Early BPC 157 studies demonstrated endothelium maintenance. Initially, this was in the context of alcohol-induced gastric lesions [146], and later in models of thrombosis and prolonged bleeding, including rat abdominal aorta anastomosis [67], anticoagulant (heparin, warfarin) and antiplatelet exposure [68,69], limb amputation, organ perforation [81,142], vessel occlusion [71,72,73,74,75,76,77], severe injury induction [78,79,80,81], and agents’ application [82,83,84,85,86,87] in occlusion/occlusion-like syndromes [71,72,73,74,75,76,77,78,79,80,81,82,83,84,85,86,87]. These models also included NO/NOS dysregulation, with L-NAME or L-arginine, and conditions where hemorrhage and thrombosis occurred simultaneously [69,85]. BPC 157 restored thrombocyte function without affecting coagulation pathways [70] and counteracted NSAID-induced prostaglandin dysfunction [88].
The dual therapeutic effect of BPC 157, context-dependent, aligns with the four sequential phases of physiological wound healing: (i) vascular constriction, (ii) loose platelet plug formation, (iii) fibrin mesh stabilization, and (iv) clot resolution with restoration of vascular patency [143,144,145,147]. Effective wound healing, therefore, inherently supports early hemostasis, thrombus formation, and timely clot dissolution. Failure in any phase can result in persistent hemorrhage or pathological thrombosis, highlighting that bleeding and thrombosis are not opposing events but temporally and functionally linked stages of the repair process [145]. This principle establishes the therapeutic design requirement for phase-sensitive, cytoprotective interventions with robust wound healing capacity as the primary endpoint.
Experimental evidence (decreased hemorrhage, decreased thrombosis) confirms BPC 157’s potent wound healing activity across multiple tissues and injury types. These include skin wounds, deep burns [53,54,63,148,149,150,151,152], tendons [50,51,153,154,155,156,157,158], ligaments [159], muscle injuries [47,158,160,161,162,163], osteotendinous and myotendinous junctions [153,154,157,164], and muscle-to-bone attachments [165]. Corneal ulcer healing, including restoration of transparency and counteraction of neovascularization, further exemplifies its multi-tissue efficacy [21,22,23,26,166]. Internal wound repair is also robust, as demonstrated by recovery of anastomoses [167] and fistulas [168], both external [169,170,171,172,173] and internal [174,175,176,177]. These outcomes confirm early hemostasis, subsequent clot removal, and microvascular restoration.
Overall, BPC 157’s systemic wound healing capacity substantiates its dual role in decreasing hemorrhage and thrombosis and provides a conceptual and experimental framework for evaluating other cytoprotective agents, though none match its comprehensive efficacy.
Notably, as part of the increasing interest for soft tissue injuries healing and BPC 157 efficacy, several reviews have recently appeared [178,179,180,181,182,183,184,185,186,187,188,189,190].
3.2. Cytoprotective Effects of Prostaglandins, Statins, ACE Inhibitors, Beta Blockers, Ca Channel Blockers, and NO Modulators as Possibilities for Wound Healing
When examined from the perspective of other pharmacological agents that exhibit partial cytoprotective or pleiotropic effects, supportive evidence for wound healing is present but notably inconsistent. Unlike BPC 157, these agents were not developed as cytoprotective therapies and do not uniformly engage the coordinated, multistage repair program required for effective wound healing.
Prostaglandins, which historically represent the first mediators of the cytoprotection concept, demonstrate a biphasic influence on wound repair [191]. Under physiological conditions, prostaglandins generally promote healing through vasodilation, angiogenesis, and epithelial restitution [192,193,194]. However, excessive prostaglandin signaling—particularly elevated PGE2—may exacerbate inflammation, fibrosis, and scarring, resulting in impaired or dysregulated healing [195].
Statins also exhibit dose- and context-dependent effects. At low-to-moderate doses, statins may enhance wound healing via anti-inflammatory actions, endothelial stabilization, and improved nitric oxide bioavailability. In contrast, higher doses have been associated with delayed tissue repair, likely due to excessive inhibition of cellular proliferation and prenylation pathways essential for regeneration [196].
ACE inhibitors generally support wound healing, presumably through improved microcirculation, bradykinin-mediated vasodilation, and modulation of inflammatory responses [197,198,199].
Beta blockers exhibit complex effects: while some studies report accelerated wound closure—possibly through reduced stress signaling and catecholamine effects—others report delayed healing, reflecting interference with perfusion, angiogenesis, or keratinocyte migration [200,201,202,203,204].
Calcium channel blockers are more consistently associated with improved wound healing, likely through enhanced microvascular perfusion, reduced vasospasm, and favorable effects on fibroblast and endothelial function [205,206,207,208,209,210,211].
Nitric oxide (NO) plays a central physiological role in wound repair, regulating angiogenesis, inflammation, fibroblast activity, collagen deposition, and re-epithelialization [212,213]. Accordingly, NO donors and restoration of nitric oxide synthase (NOS) activity accelerate wound closure [214,215,216], whereas NOS inhibition or NO deficiency delays healing, establishing NO modulation as a pro-healing strategy [217,218,219].
Overall, although these agents can influence selected components of wound repair, their effects are heterogeneous, dose-dependent, and mechanistically restricted, lacking the coordinated control of all of the phases of healing that are characteristic of true cytoprotection.
3.3. Prostaglandins, Statins, ACE Inhibitors, Beta Blockers, Ca Channel Blockers, and NO Modulators: Wound Healing as an Inconsistent Resolving Principle for Hemorrhage/Thrombosis Therapy
When the wound-healing capacity of these agents is examined in relation to the proposed cytoprotection principle linking enhanced healing with reduced hemorrhage and thrombosis (↑ wound healing = ↓ hemorrhage and ↓ thrombosis), the relationship proves inconsistent and context dependent. Unlike BPC 157, these agents do not reliably translate partial wound-healing effects into balanced hemostatic normalization.
Prostaglandins, despite their pro-healing actions, may increase bleeding risk through platelet inhibition and vasodilation [220,221,222]. Prostacyclin analogs such as iloprost are clinically used to prevent thrombosis in peripheral vascular disease and dialysis grafts, illustrating antithrombotic efficacy but at the expense of increased bleeding tendency [220].
ACE inhibitors may increase bleeding risk, particularly gastrointestinal bleeding, more frequently than angiotensin receptor blockers, consistent with bradykinin-mediated increases in vascular permeability [223,224]. Nevertheless, large cardiovascular trials demonstrate that ACE inhibitors reduce myocardial infarction and stroke incidence, indicating overall neutral or modestly antithrombotic effects [225,226,227]. Rare reports of thrombosis exist but are considered context dependent and not intrinsic pharmacological properties of this drug class [228,229].
Beta blockers generally reduce bleeding risk [229,230], yet earlier generations may reduce coronary flow at lower heart rates, potentially increasing thrombotic susceptibility [231,232]. Moreover, excessive beta blockade, as reported with sotalol overdose, may precipitate severe occlusion or occlusion-like syndromes accompanied by widespread thrombosis [84].
For calcium channel blockers, epidemiological data suggest a possible association with gastrointestinal bleeding [233], while, in patients with nonvalvular atrial fibrillation receiving oral anticoagulants and dihydropyridine, calcium channel blocker use has been associated with a higher incidence of ischemic stroke compared with non-use [234].
Statins, in contrast, are associated with reduced bleeding risk [235] and a lower incidence of venous thromboembolism in humans [236], yet these effects do not consistently align with wound-healing outcomes.
Nitric oxide represents a physiological antiplatelet and anticoagulant mediator; thus, enhancement of NO signaling, particularly at systemic or high doses, may increase bleeding risk. Conversely, NOS inhibition with L-NAME is prothrombotic, underscoring the narrow therapeutic window of NO-based modulation [237,238].
Collectively, these observations indicate that, while many pleiotropic cardiovascular agents can influence wound healing, bleeding, or thrombosis individually, they do so by shifting isolated pathways rather than restoring vascular homeostasis as an integrated process. Their inability to coordinate all four phases of wound healing—hemostasis, platelet function, fibrin stabilization, and timely clot resolution—explains why they fail to consistently resolve the hemorrhage–thrombosis paradox. This limitation sharply contrasts with the cytoprotective profile of BPC 157, which uniquely fulfills the wound-healing–hemostasis continuum as a unified therapeutic principle.
These comparative effects on wound healing, and consequently, on hemorrhage and thrombosis of prostaglandins, beta blockers, Ca channel blockers, ACE inhibitors, and NO modulators were summarized in Table 2.
Table 2.
Comparative effects of other cytoprotective/pharmacologic agents.
Thereby, as shown in Table 2, it seems that, with all mentioned agents—prostaglandins, beta blockers, Ca channel blockers, ACE inhibitors, and NO modulators—that are supposed to have some cytoprotective capabilities, and which are thereby elaborated for wound healing/hemorrhage/thrombosis relation, the ↑wound healing = ↓ hemorrhage ↓ thrombosis remains unachieved and is not combined in a consequent chain of events.
3.4. Cytoprotective Effects of Anticoagulants, Antiplatelets, and Fibrinolytics as Possibilities for Wound Healing
In contrast to BPC 157, anticoagulants, antiplatelet agents, and fibrinolytics do not consistently satisfy the principle that enhanced wound healing translates into reduced hemorrhage and reduced thrombosis. Rather than coordinating the sequential phases of vascular repair, these agents act predominantly through unidirectional interference with individual hemostatic components, thereby altering wound healing in a context- and phase-dependent, but non-integrative, manner.
Heparin illustrates this limitation. While some studies demonstrate enhanced wound healing, attributed to anti-inflammatory effects, growth factor interactions, or endothelial modulation [239,240,241], others report impaired healing, delayed epithelialization, or increased wound complications [242,243,244]. These divergent outcomes reflect the absence of phase-sensitive regulation: heparin may facilitate early events but interfere with later stabilization or remodeling phases, preventing consistent restoration of vascular integrity.
Warfarin more uniformly delays wound healing [245,246,247], consistent with its inhibition of vitamin K-dependent proteins involved in tissue repair, extracellular matrix regulation, and vascular cell survival. This effect underscores a fundamental limitation of anticoagulation strategies that suppress physiological repair mechanisms rather than modulating them.
Antiplatelet agents similarly delay wound healing [248,249,250], reflecting the impaired platelet-derived signaling required for early hemostasis, growth factor release, and subsequent tissue regeneration. Fibrinolytic agents likewise delay wound healing [251,252,253], as premature or excessive clot dissolution disrupts the scaffold formation necessary for stable repair.
Collectively, these findings indicate that conventional antithrombotic agents do not support wound healing as a unified physiological process. Instead, they selectively inhibit or exaggerate specific phases, thereby failing to integrate bleeding control, clot formation, stabilization, and resolution into a coherent reparative sequence.
3.5. Concluding Remarks on Wound Healing–Hemorrhage–Thrombosis Relations
Wound healing represents an inherent physiological organizing principle of cytoprotection, encompassing all four essential hemostatic events—vascular constriction, loose platelet plug formation, fibrin clot stabilization, and clot dissolution—which occur in a tightly regulated temporal sequence following vascular injury. Successful healing requires that each phase is initiated, supported, and terminated appropriately; failure at any stage results in persistent hemorrhage, pathological thrombosis, or defective tissue repair.
Within this framework, hemorrhage and thrombosis are not opposing pathological states but phase-dependent manifestations of the same repair process. Accordingly, the relationship ↑ wound healing = ↓ hemorrhage and ↓ thrombosis reflects restoration of physiological homeostasis rather than pharmacological suppression of coagulation or platelet activity.
The consistent observation that BPC 157 simultaneously reduces bleeding and thrombosis therefore indicates a unique capacity to integrate wound healing with hemostatic regulation. In cytoprotection terms, this implies early hemostasis when bleeding predominates, timely clot resolution when thrombosis emerges, microvascular restoration, and normalization of platelet function—without direct interference with coagulation pathways. The outcome is a balanced, phase-sensitive modulation that follows physiological repair logic.
Other agents may influence individual components of wound healing or hemostasis, but none consistently achieves both reduced hemorrhage and reduced thrombosis in a coordinated, phase-dependent manner. Thus, BPC 157 exemplifies a cytoprotective strategy that aligns therapeutic intervention with endogenous repair mechanisms, redefining hemorrhage and thrombosis as resolvable phases of vascular healing rather than mutually exclusive targets.
3.6. Concluding Remarks on Wound Healing/Hemorrhage/Thrombosis Relations and BPC 157/NO System Relation
It can also be argued that such a balance would require an applicable dual effect that can be seen in both heparin and warfarin, given that they are essential as hemorrhage models [254,255,256,257,258].
Notably, unlike BPC 157 therapy studies with both heparin and warfarin [68,69], none of the mentioned agents, sharing some cytoprotection capabilities, prostaglandins, beta blockers, Ca channel blockers, and ACE inhibitors, were tested with heparin or warfarin bleeding. Likewise, they were not used in combination with targeted modulation of the NO system.
The only direct study combining NO agents with heparin and warfarin is that with regard to the effects of BPC 157 [69]. Thereby, the formula by which BPC 157 ↑ wound healing = ↓ hemorrhage and ↓ thrombosis stands with the consistent dual context-dependent effect, on both heparin and warfarin, in which BPC 157 counteracts both L-NAME pro-thrombotic effects, as well as an L-arginine anti-coagulant effect [69]. These effects occur along with the counteraction of other effects of NO agents, i.e., L-NAME-induced hypertension, and L-arginine-induced hypotension [16,54,55,56]. Notably, such counteracting effects have occurred in a large number of targets (i.e., more than 80), suggesting a general BPC 157/NO system relation [16,56]. Additionally, BPC 157 induces the NO release, resistant to L-NAME, that counteracts the NO release induced by L-arginine [16,54,55,56]. Indicating restoration of redox balance [16], BPC 157 ↑ wound healing = ↓ hemorrhage and ↓ thrombosis correlates with the findings that BPC 157 therapy normalizes NO tissue levels, either increased or decreased, along with a counteraction of the increased MDA values [16].
In conclusion, indicative therapy occurred for hemorrhage, thrombosis, hypertension, hypotension, and thrombocytes’ function (without affecting the coagulation cascade) [16,54,55,56,67,68,69,70]. In addition, BPC 157 therapy affects signaling pathways controlling vasomotor tone [45,46,47] (VEGFR2-Akt-eNOS and Src-Caveolin-1-eNOS). At the general level, this dual (modulatory) action (i.e., either of pro-coagulant effects, anti-coagulant effects, hypertension, and hypotension reversed toward normal) also applies to the NO system’s effects as a whole [16,54,55,56,67,68,69,70]. Such a role for BPC 157 therapy could be essential amid the dual role of NO, as both an inhibition and an uncontrolled excess of NO could lead to significant damage [259,260]. Consequently, in providing the essential role of NO to wound healing [261], BPC 157’s ability to restore NO system homeostasis may represent a central mechanism underlying its wide-ranging therapeutic potential, represented as the maintained equation of ↑ wound healing = ↓ hemorrhage and ↓ thrombosis [16,45,46,47,54,55,56,67,68,69,70,145].
4. Arrhythmias
As a conceptual principle, the ↑ wound healing = ↓ hemorrhage and ↓ thrombosis principle reflects a cytoprotective agent’s ability to normalize both extremes of bleeding and thrombosis, restoring vascular homeostasis and orderly healing [145]. Arrhythmias represent another critical facet of this systemic cytoprotection, as endothelial maintenance and vascular integrity extend pleiotropic effects from cytoprotection to organoprotection [1,2,3,4,5,6,7,8,9]. Thus, as a further conceptual point, antiarrhythmic normalization is therefore claimed as an essential component of true cytoprotection [262], and BPC 157’s anti-arrhythmic potential and its counteraction of arrhythmias has been recently reviewed [262].
Arrhythmias, particularly those impairing effective cardiac contraction, promote stasis, contributing to Virchow’s triad (stasis + endothelial dysfunction + hypercoagulability) and increasing thrombotic risk [263,264,265,266,267]. Atrial fibrillation can form left atrial appendage thrombi, while ventricular arrhythmias reduce cardiac output and favor regional or systemic hypoperfusion. Endothelial injury and arrhythmia-mediated hypercoagulability may occur even without ischemia [265,266,267].
Preclinical studies show that BPC 157 counteracts a wide array of arrhythmogenic triggers, including digitalis [268], potassium overdose [269], furosemide [270], lidocaine [271], bupivacaine [272], succinylcholine [273], neuroleptics [83,274], amphetamine [83], domperidone [83], metoclopramide [274], sotalol [84], isoprenaline [85], sodium laureate [86], alcohol [87], monocrotaline [275], hyperkalemia [269,273], hypokalemia [270], hyperlithiemia [82], and various occlusion/occlusion-like syndromes [71,72,73,74,75,76,77,78,79,80,81,82,83,84,85,86,87]. These effects also include mitigation of arrhythmias aggravated by NO/NOS modulation [85,268,269,270,271,272], supported by HEK293 studies showing direct membrane stabilization [269,270,271,272,276]. Analogous to its ability to normalize both tachycardia and bradycardia [262], BPC 157 restores hemostatic and microvascular balance without direct pro- or anticoagulant activity, integrating arrhythmia control with reduced hemorrhage and thrombosis. Notably, this could also be mobilized against a thrombus via the use of antiarrhythmics, and against hemorrhage in particular, because anticoagulants are utilized as part of an antiarrhythmic application [277,278,279,280]. Notably, as mentioned, BPC 157 is effective against sodium laurate intravenous administration [86]. This can be, as suggested, a cytoprotective therapy that preserves endothelial integrity and microvascular homeostasis [262].
Comparative pharmacology highlights BPC 157’s uniqueness. Intrinsic sympathomimetic β blockers can normalize heart rate bidirectionally [281,282,283], whereas Ca channel blockers modulate heart rate directionally—non-dihydropyridines may induce bradycardia and dihydropyridines may provoke reflex tachycardia—but lack self-normalizing capability [284,285]. ACE inhibitors and prostaglandins may modestly alter heart rate via reflex sympathetic activation [286,287,288]. NO donors or L-arginine enhance vagal tone and limit tachycardia, while NOS inhibition (L-NAME) promotes tachycardia and hypertension [289,290,291]. Statins can reduce elevated heart rates and improve autonomic balance without inducing bradycardia [292,293,294,295,296,297].
In summary, BPC 157 uniquely integrates cytoprotection across wound healing, hemostasis, thrombosis, and arrhythmias by restoring endothelial function, stabilizing cardiac electrical activity, and maintaining microvascular homeostasis. Its effects are context-dependent, bidirectional, and phase-sensitive, exemplifying the systemic principle that functional normalization—not mere inhibition or activation—underlies the resolution of hemorrhage and thrombosis.
5. Virchow Triad
Thrombohemorrhagic disorders, as emphasized in Section 2.7, can present with both thrombosis and hemorrhage simultaneously. Early cytoprotection studies have demonstrated that endothelial lesions, thrombus formation, and stasis precede gastric epithelial hemorrhagic lesions [4,5,6,7], implying that Virchow’s triad conditions co-occur with hemorrhage during lesion development. Consequently, cytoprotection and Virchow triad circumstances are closely linked [16,17,18,19,20,21,22,23,24,25,26], even if not explicitly framed as such initially [4,5,6,7]. As a final conceptual point, the logical extension is that cytoprotective agents, by resolving these conditions, can achieve a ↓ Virchow triad = ↓ hemorrhage + ↓ thrombosis equation, complementing the other cytoprotective principles, ↑ wound healing = ↓ hemorrhage + ↓ thrombosis and ↓ arrhythmias = ↓ hemorrhage + ↓ thrombosis [16,17,18,19,20,21,22,23,24,25,26].
BPC 157 therapy has been systematically evaluated in a broad spectrum of occlusion/occlusion-like models [71,72,73,74,75,76,77,78,79,80,81,82,83,84,85,86,87], where it consistently reversed severe vascular and multiorgan failure. Models included major vessel occlusion [74,75,76,77], bile duct occlusion with acute pancreatitis [80], intra-abdominal hypertension grade III–IV [78,79], ischemia-reperfusion injury [78,79], organ perforation [81], and exposure to cytotoxic agents such as lithium [82], intragastric alcohol [87], intravenous sodium laurate [86], isoprenaline [85], sotalol [84], neuroleptics [83], and amphetamine [83]. With BPC 157 therapy, the described ↓ Virchow triad circumstances = ↓ hemorrhage and ↓ thrombosis equation also occurs with the reversal of Pringle maneuver ischemia–reperfusion [71], Budd–Chiari syndrome models [72], and inferior caval vein ligation [73].
Restoring vascular patency, microcirculation, and endothelial integrity means that BPC 157 promptly counteracts hemorrhage and thrombosis, peripherally and centrally. This means reversing secondary lesions in the brain, heart, lung, liver, kidney, and gastrointestinal tract. Likewise, this means attenuation/elimination of various arrhythmias (bradycardias and tachycardias); intracranial, portal, and caval hypertension; and aortal hypotension. The particular reversal includes the major vessels that had failed, the inferior caval vein and superior mesenteric vein, which were congested, and the aorta and azygos vein, which were collapsed [74,75,76,77,78,79,80,81,82,83,84,85,86,87], all of which fully recovered (i.e., azygos vein activated, direct blood flow delivery). The circumstances of Virchow’s triad are regularly reversed.
A key mechanistic feature is collateral vessel recruitment, particularly the azygos vein, which rapidly redistributes venous blood when primary pathways are blocked, alleviating venous hypertension and arterial hypotension. BPC 157 also stabilizes endothelial and cardiac membranes, acts as a free radical scavenger, and maintains cellular junctions, counteracting “leaky gut” phenomena [44,145]. These vascular protective effects are closely linked to the NO system, with BPC 157 normalizing NO levels, mitigating both L-NAME-induced prothrombotic effects and L-arginine-induced hypotension/anti-coagulation [16,54,55,56,69]. Rapid vascular wall remodeling, evidenced by FTIR studies, occurs in parallel with restored perfusion, and may be responsible for the noted chain of events, commonly counteracted (i.e., resolved bradycardia or tachycardia, and reversal of peripheral and central hemorrhage and thrombosis) [298,299].
As emphasized before, these therapy effects occur even while the underlying insult persists (i.e., occlusion of major blood vessels [71,72,73,74,75,76,77], increased intra-abdominal pressure [78], grade III, grade IV) or the injury is already highly advanced and fully established [79]. This indicates a functional action at the final common pathway, whatever the molecular construct [43,44,45,46,47,48,49,50,51,52,53,54]. This explains BPC 157’s therapeutic effects, fully specified, i.e., in inferior caval vein syndrome (induced by infrarenal ligation of inferior caval vein), where there is a counteraction of the full syndrome [73]. This includes cases where there is a direct vein injury, thrombosis, thrombocytopenia, and prolonged bleeding. Rapid presentation of collaterals means instant redistribution of the trapped blood volume amid counteracted venous hypertension and arterial hypotension and tachycardia. This occurs with counteraction of oxidative stress (as a result of the lysis of endothelial cells [73]) and low NO level in the inferior caval vein. Particular gene expression (i.e., EGR, NOS, SRF, VEGR, AKT1, PLCɣ, KRAS) appears as a likely special point to explain how the dysfunction and its counteraction are causal to or a result of each other [73].
Importantly, the BPC 157 effect is conditional and context-dependent, appearing even with established and severe insults, such as complete vascular occlusion or advanced highly increased intra-abdominal pressure (grade III, grade IV), highlighting action at a final common pathway irrespective of the initial molecular insult [43,44,45,46,47,48,49,50,51,52,53,54]. Molecular studies implicate the modulation of critical signaling pathways, including VEGFR2-Akt-eNOS and Src-Caveolin-1-eNOS, supporting vasomotor tone regulation and endothelial recovery [16,45,46,47,54,55,56,67,68,69,70]. These effects occur without the need for exogenous ligands or shear stress, suggesting a direct interaction of BPC 157 with cellular targets and gasotransmitter pathways [300].
In contrast, comparative cytoprotective agents—prostaglandins, beta blockers, Ca channel blockers, ACE inhibitors, and statins—have not been tested in these occlusion/occlusion-like models. Thus, BPC 157 uniquely demonstrates a consistent ability to reverse Virchow’s triad, while simultaneously normalizing hemodynamic parameters and microvascular perfusion.
The convergence of the three cytoprotective principles—↑ wound healing, ↓ arrhythmias, and ↓ Virchow triad—suggests that BPC 157 functions as a system-level modulator, rather than a single-pathway pharmacologic agent. By integrating endothelial stabilization, collateral recruitment, NO system homeostasis, oxidative stress reduction, and vasomotor regulation, BPC 157 achieves bidirectional, phase-sensitive restoration of vascular homeostasis without pushing physiology toward either extreme [16].
This BPC 157 hemorrhage/thrombosis relation is summarized in Table 3.
Table 3.
Summary of counteraction of hemorrhage and thrombosis by stable gastric pentadecapeptide BPC 157 in rats. Notably, as a common point, in occlusion/occlusion-like syndromes [74,75,76,77,78,79,80,81,82,83,84,85,86,87] counteraction includes the severe lesions in the brain, heart, lung, liver, kidney, and gastrointestinal tract; attenuation/elimination of various arrhythmias; intracranial, portal, and caval hypertension; and aortal hypotension. Attenuation/elimination occurs with prompt attenuation/elimination of hemorrhage and thrombosis occurring peripherally and centrally. The particular reversal includes the major vessels that had failed—the inferior caval vein and the superior mesenteric vein, which were congested, and the aorta and azygos vein, which were collapsed [74,75,76,77,78,79,80,81,82,83,84,85,86,87]—and which all fully recovered (i.e., azygos vein activated, direct blood flow delivery).
Likewise, being native and stable in human gastric juice (more than 24 h) while acting as a cytoprotective mediator likely allows for the translation of the maintenance of the gastrointestinal mucosa to other organ therapies, broadening the practical applicability of this peptide (i.e., pleiotropic beneficial effects, which are always applied alone without carrier), including per-oral application [16,17,18,19,20,21,22,23,24,25,26,145,262,301]. Given the consistent beneficial effects so far presented in the mentioned studies, BPC 157 therapy could specifically counteract the cytotoxic and damaging actions of NO, being organ specific. This might be seen as a network of evidence for the physiological significance of the revealed BPC 157/NO system interplay. Notably, BPC 157, native and stable in human gastric juice, was found in in situ hybridization and immunostaining studies in humans to be largely distributed in tissues [16,145,262,301] and may have additional physiological regulatory roles [16,17,18,19,20,21,22,23,24,25,26,145,301] when released from the stomach and sent to other organs. These points, and further application (i.e., efficacy and the lack of adverse effects in limited clinical trials [58,59,60,61,64,65,66]), are supported by the lack of adverse effects in toxicology studies. Notably, for BPC 157, an effective range within 10 µg–10 ng/kg means full confirmation [62,63] that a lethal dose (LD1) was not reached even at 2 g/kg i.v. or i.g. (a harmless limit test, without adverse effects in rodents) (Figure 2).
Figure 2.
Summary of hypothesized theoretical cytoprotection framework. It is suggested that cytoprotection can be a theoretical unifying concept for the counteraction of hemorrhage and of thrombosis. Notably, as a cytoprotection mediator, BPC 157 therapy counteracts prolonged bleeding, organ hemorrhage, and thrombosis in rats, peripherally and centrally, without influencing the coagulation cascade (aggregometry and thromboelastometry studies). Counteraction of both hemorrhage and thrombosis raises a theoretical and practical query: how a useful cytoprotective therapy could support the logistical question of the “ideal agent”, also with conventional anticoagulants, antiplatelets, and fibrinolytics (≈partial cytoprotection/narrow range), and with other agents found to share some of the cytoprotective properties, prostaglandins, ACE inhibitors, beta blockers, Ca channel blockers, NO modulators, and statins (≈partial cytoprotection/more extended range). Considering hemorrhage and thrombosis, when both involved, the effects on wound healing, arrhythmias, and Virchow triad circumstances were considered as key proofs of the agent’s counteracting activity (green tick marks) on either hemorrhage or thrombosis, or the counteraction of both hemorrhage and thrombosis. Only BPC 157 demonstrates well-matched cytoprotective hemorrhage/thrombosis effects, BPC 157 ≈ full cytoprotection/wide-range homeostasis. As a concept proof ↓ hemorrhage + ↓ thrombosis, it fulfills all three converging resolving principles: ↑ Wound healing = ↓ hemorrhage + ↓ thrombosis; ↓ Arrhythmia = ↓ hemorrhage + ↓ thrombosis; ↓ Virchow triad = ↓ hemorrhage + ↓ thrombosis (see also Table 4). Nevertheless, in preclinical models, stable gastric pentadecapeptide BPC 157, in the clinic, has predominantly demonstrated a lack of adverse effects in available human trials to date. As a prominent cytoprotection mediator (LD1 not achieved in toxicology studies), it is capable of restoring vascular homeostasis, representing a novel therapeutic strategy that integrates hemostasis, endothelial protection, and functional tissue repair [16,17,18,19,20,21,22,23,24,25,26,145,262].
Finally, Table 4 expresses a summary of the converging resolving principles when cytoprotection was found to decrease hemorrhage and thrombosis as phase-dependent outcomes of the counteracted vascular dysregulation carried out by BPC 157 therapy.
Table 4.
Converging resolving principles of BPC 157 therapy.
6. Limitations and Future Directions
Some final notations must emphasize the complexity of the problem of the hemorrhage–thrombosis paradox as an inherent limitation for any review.
In general, there is still a dominance of one group within the presented papers [16,17,18,19,20,21,22,23,24,25,26,145,262,301]. Additionally, and in general, the cytoprotection concept [1,2,3,4,5,6,7,8,9], as a concept, is still not implemented in clinics. Taken as a hypothesis-based interpretive model (i.e., “ideal” agent capable of bidirectional regulation), it is elaborated that BPC 157 and other agents have been found to share some cytoprotective properties. Finally, decreased hemorrhage, decrease thrombosis determination goes through three converging resolving principles—wound, arrhythmias, and Virchow triad—meaning ↑ wound healing = ↓ hemorrhage + ↓ thrombosis; ↓ arrhythmia = ↓ hemorrhage + ↓ thrombosis; and ↓ Virchow triad = ↓ hemorrhage + ↓ thrombosis. All evidence combined can provide a unified systems-level model focused on BPC 157.
However, together, these could still oversimplify the multifaceted nature of the hemorrhage/thrombosis issue. Nevertheless, reliance on preclinical models necessitates further clinical validation.
Likewise, and also in general, thrombus formation and the severity, timing, and nature of blood loss—conditions that are almost impossible to standardize in clinical (human) settings—have been examined using rat models. However, it may be that a rat model simplifies these variables, which is scientifically useful but limits direct clinical predictability [302,303,304,305].
Finally, it remains to be seen whether the evidence derived from the majority of experimental work (i.e., initial discovery, mechanistic exploration, and model validation) [16,17,18,19,20,21,22,23,24,25,26,145,262,301] is found within a single research group, providing that it aligns with the confirmatory reports of other groups (i.e., [45,46,47,48,49,50,51,52,53,54,306,307,308,309,310,311,312,313]). In many studies, translational values have emphasized the similar therapeutic effect obtained by different manners of administration in the same model [16,17,18,19,20,21,22,23,24,25,26,145,262,301]. In addition to the clinical data (although still limited), studies have included favorable safety reports [58,59,60,61,62,63,64,65,66] that are comparable with previous notations [16].
There is also a need to search for a resolving analogy (preclinical models → further clinical validation). Although likely hypothetical, and not a substitute for the rigorous clinical validation that should be undertaken, such a pattern agrees with what that has been historically observed with a favorable outcome. Notably, this has already occurred, during the early preclinical phases of several now-established therapies, including the erythropoietin (EPO) [314,315] and glucagon-like peptide-1 (GLP-1) analogs before industrial expansion [316,317,318], and neuropeptides such as pituitary adenylate cyclase-activating polypeptide (PACAP) [319] and vasoactive intestinal peptide (VIP) [320,321].
7. Conclusions
This review addresses the hemorrhage/thrombosis ideal agent problem from a cytoprotective perspective (decreased hemorrhage and thrombosis to preserve and reestablish homeostasis). It proposes the stable gastric pentadecapeptide BPC 157, which acts as a cytoprotective mediator. In rodents, BPC 157 can simultaneously counteract hemorrhage and thrombosis without directly affecting the coagulation cascade (aggregometry, thromboelastometry). Within this framework, presenting both hemorrhage and thrombosis that should be both counteracted, the manuscript synthesizes conceptual, experimental, and clinical evidence. BPC 157’s effective wound healing, arrhythmia control, and normalization of Virchow’s triad represent converging physiological processes for the realization of the principle of decreased hemorrhage and decreased thrombosis to preserve and reestablish homeostasis.
As a comparison from a cytoprotective (partial vs. full) standpoint, conventional agents—including anticoagulants, antiplatelet drugs, fibrinolytics, beta blockers, calcium channel blockers, prostaglandins, NO modulators, ACE inhibitors, and statins—provide only partial, context-dependent protection, typically unidirectional, dose-limited, or achieved at the expense of opposing pathological risks. In contrast, preclinical evidence indicates that BPC 157 functions as a vasoprotective cytoprotective mediator capable of bidirectional regulation. Its effects likely involve the preservation of endothelial integrity, the normalization of microcirculation, the modulation of the NO system, the stabilization of hemostatic balance, and the recruitment of adaptive collateral pathways. Accordingly, with the potential limitations of conceptual points and those regarding preclinical predominance, the relationships among wound healing, arrhythmia control, and Virchow triad normalization may be viewed as interconnected cytoprotective principles contributing to the reduction of both hemorrhage and thrombosis.
Importantly, BPC 157 can counteract the bleeding induced by anticoagulants or antiplatelet agents, while simultaneously mitigating organ hemorrhage and thrombosis under conditions of vascular occlusion or arrhythmia. These properties suggest that wound healing is not merely a local reparative process, but a central organizing principle of systemic vascular homeostasis. Combined with its oral bioavailability, gastric stability, high safety profile, and efficacy in both prophylactic and therapeutic settings, BPC 157 holds substantial translational potential as a novel cytoprotective strategy for complex vascular and hemostatic disorders.
Author Contributions
M.L.B., M.L. and I.P.M.: Conceptualization; I.B., D.B. and L.B.O.: Methodology; P.S., G.Z.P. and A.S.: Writing—original draft preparation, review and editing; A.B.B., A.T. and S.S. (Sven Seiwerth): Writing—review and editing; M.S. Visualization; M.U., V.S., and S.S. (Suncana Sikiric): Investigation; L.K., D.S. and S.U.: Formal analysis; H.V. and L.T.: Data curation; M.K., I.K. and S.S. (Sanja Strbe): Validation. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by the University of Zagreb, Zagreb, Croatia (Grant BM 10106-22-3071).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Robert, A. Cytoprotection by prostaglandins. Gastroenterology 1979, 77, 761–767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Robert, A. Current history of cytoprotection. Prostaglandins 1981, 21, 89–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Robert, A.; Nezamis, J.E.; Lancaster, C.; Davis, J.P.; Field, S.O.; Hanchar, A.J. Mild irritants prevent gastric necrosis through “adaptive cytoprotection” mediated by prostaglandins. Am. J. Physiol. 1983, 245, G113–G121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szabo, S. Role of sulfhydryls and early vascular lesions in gastric mucosal injury. Acta Physiol. Hung. 1984, 64, 203–214. [Google Scholar] [PubMed]
- Trier, J.S.; Szabo, S.; Allan, C.H. Ethanol-induced damage to mucosal capillaries of rat stomach. Ultrastructural features and effects of prostaglandin F2β and cysteamine. Gastroenterology 1987, 92, 13–22. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pihan, G.; Majzoubi, D.; Haudenschild, C.; Trier, J.S.; Szabo, S. Early microcirculatory stasis in acute gastric mucosal injury in the rat and prevention by 16,16-dimethyl prostaglandin E2 or sodium thiosulfate. Gastroenterology 1986, 91, 1415–1426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szabo, S.; Trier, J.S.; Brown, A.; Schnoor, J. Early vascular injury and increased vascular permeability in gastric mucosal injury caused by ethanol in the rat. Gastroenterology 1985, 88, 228–236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szabo, S. Experimental basis for a role for sulfhydryls and dopamine in ulcerogenesis: A primer for cytoprotection-organoprotection. Klin. Wochenschr. 1986, 64, 116–122. [Google Scholar] [PubMed]
- Szabo, S.; Usadel, K.H. Cytoprotection-organoprotection by somatostatin: Gastric and hepatic lesions. Experientia 1982, 38, 254–256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gale, A.J. Continuing education course #2: Current understanding of hemostasis. Toxicol. Pathol. 2011, 39, 273–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Furie, B.; Furie, B.C. Mechanisms of thrombus formation. N. Engl. J. Med. 2008, 359, 938–949. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Linkins, L.-A.; Choi, P.T.; Douketis, J.D. Clinical impact of bleeding in patients taking oral anticoagulant therapy for venous thromboembolism. Ann. Intern. Med. 2003, 139, 893–900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levi, M.; Levy, J.H.; Andersen, H.F.; Truloff, D. Safety of recombinant activated factor VII in randomized clinical trials. N. Engl. J. Med. 2010, 363, 1791–1800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoffman, M.; Monroe, D.M. A cell-based model of hemostasis. Thromb. Haemost. 2001, 85, 958–965. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mackman, N. Triggers, targets and treatments for thrombosis. Nature 2008, 451, 914–918. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Seiwerth, S.; Skrtic, A.; Staresinic, M.; Strbe, S.; Vuksic, A.; Sikiric, S.; Bekic, D.; Soldo, D.; Grizelj, B.; et al. Stable gastric pentadecapeptide BPC 157 as a therapy and safety key: A special beneficial pleiotropic effect controlling and modulating angiogenesis and the NO-system. Pharmaceuticals 2025, 18, 928. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Seiwerth, S.; Skrtic, A.; Staresinic, M.; Strbe, S.; Vuksic, A.; Sikiric, S.; Bekic, D.; Penovic, T.; Drazenovic, D.; et al. Acute compartment syndrome and intra-abdominal hypertension, decompression, current pharmacotherapy, and stable gastric pentadecapeptide BPC 157 solution. Pharmaceuticals 2025, 18, 866. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Sever, M.; Krezic, I.; Vranes, H.; Kalogjera, L.; Smoday, I.M.; Vukovic, V.; Oroz, K.; Coric, L.; Skoro, M.; et al. New studies with stable gastric pentadecapeptide protecting gastrointestinal tract. Significance of counteraction of vascular and multiorgan failure of occlusion/occlusion-like syndrome in cytoprotection/organoprotection. Inflammopharmacology 2024, 32, 3119–3161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Boban Blagaic, A.; Strbe, S.; Beketic Oreskovic, L.; Oreskovic, I.; Sikiric, S.; Staresinic, M.; Sever, M.; Kokot, A.; Jurjevic, I.; et al. The stable gastric pentadecapeptide BPC 157 pleiotropic beneficial activity and its possible relations with neurotransmitter activity. Pharmaceuticals 2024, 17, 461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Gojkovic, S.; Knezevic, M.; Tepes, M.; Strbe, S.; Vukojevic, J.; Duzel, A.; Kralj, T.; Krezic, I.; Zizek, H.; et al. Stable gastric pentadecapeptide BPC 157: Prompt particular activation of collateral pathways. Curr. Med. Chem. 2023, 30, 1568–1573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Kokot, A.; Kralj, T.; Zlatar, M.; Masnec, S.; Lazic, R.; Loncaric, K.; Oroz, K.; Sablic, M.; Boljesic, M.; et al. Stable gastric pentadecapeptide BPC 157—Possible novel therapy of glaucoma and other ocular conditions. Pharmaceuticals 2023, 16, 1052. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Staresinic, M.; Japjec, M.; Vranes, H.; Prtoric, A.; Zizek, H.; Krezic, I.; Gojkovic, S.; Smoday, I.M.; Oroz, K.; Staresinic, E.; et al. Stable gastric pentadecapeptide BPC 157 and striated, smooth, and heart muscle. Biomedicines 2022, 10, 3221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Udovicic, M.; Barisic, I.; Balenovic, D.; Zivanovic Posilovic, G.; Strinic, D.; Uzun, S.; Sikiric, S.; Krezic, I.; Zizek, H.; et al. Stable gastric pentadecapeptide BPC 157 as useful cytoprotective peptide therapy in the heart disturbances, myocardial infarction, heart failure, pulmonary hypertension, arrhythmias, and thrombosis presentation. Biomedicines 2022, 10, 2696. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Skrtic, A.; Gojkovic, S.; Krezic, I.; Zizek, H.; Lovric, E.; Sikiric, S.; Knezevic, M.; Strbe, S.; Milavic, M.; et al. Cytoprotective gastric pentadecapeptide BPC 157 resolves major vessel occlusion disturbances, ischemia-reperfusion injury following Pringle maneuver, and Budd-Chiari syndrome. World J. Gastroenterol. 2022, 28, 23–46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Seiwerth, S.; Skrtic, A.; Staresinic, M.; Strbe, S.; Vuksic, A.; Sikiric, S.; Bekic, D.; Soldo, D.; Grizelj, B.; et al. BPC 157 Therapy: Targeting angiogenesis and nitric oxide’s cytotoxic and damaging actions, but maintaining, promoting, or recovering their essential protective functions. Comment on Józwiak et al. Multifunctionality and Possible Medical Application of the BPC 157 Peptide—Literature and Patent Review. Pharmaceuticals 2025, 18, 1450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Masnec, S.; Kokot, A.; Kralj, T.; Zlatar, M.; Loncaric, K.; Sablic, M.; Kalauz, M.; Beslic, I.; Oroz, K.; Mrvelj, B.; et al. Challenge of corneal ulcer healing: A novel conceptual framework, the “triad” of corneal ulcer healing/corneal neovascularization/intraocular pressure, and avascular tendon healing, for evaluation of corneal ulcer therapy, therapy of neovascularization, glaucoma therapy, and pentadecapeptide BPC 157 efficacy. Pharmaceuticals 2025, 18, 1822. [Google Scholar] [CrossRef] [Scilit]
- Niki, E.; Noguchi, N.; Tsuchihashi, H.; Gotoh, N. Interaction among vitamin C, vitamin E, and β-carotene. Am. J. Clin. Nutr. 1995, 62, 1322S–1326S. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liguori, I.; Russo, G.; Curcio, F.; Bulli, G.; Aran, L.; Della-Morte, D.; Gargiulo, G.; Testa, G.; Cacciatore, F.; Bonaduce, D.; et al. Oxidative stress, aging, and diseases. Clin. Interv. Aging 2018, 13, 757–772. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Belenichev, I.; Popazova, O.; Bukhtiyarova, N.; Savchenko, D.; Oksenych, V.; Kamyshnyi, O. Modulating nitric oxide: Implications for cytotoxicity and cytoprotection. Antioxidants 2024, 13, 504. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Shahin, Y.; Khan, J.A.; Samuel, N.; Chetter, I. Angiotensin converting enzyme inhibitors effect on endothelial dysfunction: A meta-analysis of randomised controlled trials. Atherosclerosis 2011, 216, 7–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, J.K.; Laufs, U. Pleiotropic effects of statins. Annu. Rev. Pharmacol. Toxicol. 2005, 45, 89–118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davignon, J. Beneficial cardiovascular pleiotropic effects of statins. Circulation 2004, 109, III39–III43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, C.; Hu, Y.; Hou, L.; Ju, J.; Li, X.; Du, N.; Guan, X.; Liu, Z.; Zhang, T.; Qin, W.; et al. β-Blocker carvedilol protects cardiomyocytes against oxidative stress-induced apoptosis by up-regulating miR-133 expression. J. Mol. Cell. Cardiol. 2014, 75, 111–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakamura, K.; Murakami, M.; Miura, D.; Yunoki, K.; Enko, K.; Tanaka, M.; Saito, Y.; Nishii, N.; Miyoshi, T.; Yoshida, M.; et al. Beta-blockers and oxidative stress in patients with heart failure. Pharmaceuticals 2011, 4, 1088–1100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mason, R.P.; Mak, I.T.; Walter, M.F.; Tulenko, T.N.; Mason, P.E. Antioxidant and cytoprotective activities of the calcium channel blocker mibefradil. Biochem. Pharmacol. 1998, 56, 1239–1246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deakin, C.D.; Fagan, E.A.; Williams, R. Cytoprotective effects of calcium channel blockers: Mechanisms and potential applications in hepatocellular injury. J. Hepatol. 1991, 12, 251–255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evrova, O.; Kellenberger, D.; Calcagni, M.; Vogel, V.; Buschmann, J. Supporting cell-based tendon therapy: Effect of PDGF-BB and ascorbic acid on rabbit Achilles tenocytes in vitro. Int. J. Mol. Sci. 2020, 21, 458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaji, D.A.; Howell, K.L.; Balic, Z.; Hubmacher, D.; Huang, A.H. TGFβ signaling is required for tenocyte recruitment and functional neonatal tendon regeneration. eLife 2020, 9, e51779. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Lu, J.; Jiang, L.; Chen, Y.; Lyu, K.; Zhu, B.; Li, Y.; Liu, X.; Liu, X.; Long, L.; Wang, X.; et al. The functions and mechanisms of basic fibroblast growth factor in tendon repair. Front. Physiol. 2022, 13, 852795. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liang, M.; Cornell, H.R.; Zargar Baboldashti, N.; Thompson, M.S.; Carr, A.J.; Hulley, P.A. Regulation of hypoxia-induced cell death in human tenocytes. Adv. Orthop. 2012, 2012, 984950. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Scott, A.; Khan, K.M.; Duronio, V. IGF-I activates PKB and prevents anoxic apoptosis in Achilles tendon cells. J. Orthop. Res. 2005, 23, 1219–1225. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Z.; Shen, X.; Cao, L.; Yuan, Z.; Chen, S.; Zheng, X.; Tang, M.; Lee, K.K.; Cai, D. Bone morphogenetic protein 2 improves patellar tendon healing by promoting migration and proliferation of tenocytes. Chin. Sci. Bull. 2011, 56, 1361–1369. [Google Scholar] [CrossRef] [Scilit]
- Kang, E.A.; Han, Y.M.; An, J.M.; Park, Y.J.; Sikiric, P.; Kim, D.H.; Kwon, K.A.; Kim, Y.J.; Yang, D.; Tchah, H.; et al. BPC157 as potential agent rescuing from cancer cachexia. Curr. Pharm. Des. 2018, 24, 1947–1956. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, J.M.; Lee, H.J.; Sikiric, P.; Hahm, K.B. BPC157 rescued NSAID-cytotoxicity via stabilizing intestinal permeability and enhancing cytoprotection. Curr. Pharm. Des. 2020, 26, 2971–2981. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, H.; Wei, M.; Li, N.; Lu, Q.; Shrestha, S.M.; Tan, J.; Zhang, Z.; Wu, G.; Shi, R. Clopidogrel-induced gastric injury in rats is attenuated by stable gastric pentadecapeptide BPC 157. Drug Des. Dev. Ther. 2020, 14, 5599–5610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, M.J.; Lee, C.H.; Chueh, H.Y.; Chang, G.J.; Huang, H.Y.; Lin, Y.; Pang, J.H.S. Modulatory effects of BPC 157 on vasomotor tone and the activation of Src–caveolin-1–endothelial nitric oxide synthase pathway. Sci. Rep. 2020, 10, 17078. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, M.J.; Liu, H.T.; Wang, C.N.; Huang, H.Y.; Lin, Y.; Ko, Y.S.; Wang, J.S.; Chang, V.H.S.; Pang, J.H.S. Therapeutic potential of pro-angiogenic BPC157 is associated with VEGFR2 activation and up-regulation. J. Mol. Med. 2017, 95, 323–333. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, B.S.; Huang, S.C.; Chen, F.H.; Chang, Y.; Mei, H.F.; Huang, H.Y.; Chen, W.Y.; Pang, J.S. Pentadecapeptide BPC 157 efficiently reduces radiation-induced liver injury and lipid accumulation through Kruppel-like factor 4 upregulation both in vivo and in vitro. Life Sci. 2022, 310, 121072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.Y.; Qu, M.; Duan, R.; Shi, D.; Jin, L.; Gao, J.; Wood, J.D.; Li, J.; Wang, G.D. Cytoprotective mechanism of the novel gastric peptide BPC157 in gastrointestinal tract and cultured enteric neurons and glial cells. Neurosci. Bull. 2019, 35, 167–170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, C.H.; Tsai, W.C.; Hsu, Y.H.; Pang, J.H.S. Pentadecapeptide BPC 157 enhances the growth hormone receptor expression in tendon fibroblasts. Molecules 2014, 19, 19066–19077. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, C.H.; Tsai, W.C.; Lin, M.S.; Hsu, Y.H.; Pang, J.H.S. The promoting effect of pentadecapeptide BPC 157 on tendon healing involves tendon outgrowth, cell survival, and cell migration. J. Appl. Physiol. 2011, 110, 774–780. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Radeljak, S.; Seiwerth, S.; Sikiric, P. BPC 157 inhibits cell growth and VEGF signalling via the MAPK kinase pathway in the human melanoma cell line. Melanoma Res. 2004, 14, A14–A15. [Google Scholar] [CrossRef] [Scilit]
- Ivetić Tkalcević, V.; Cuzić, S.; Brajsa, K.; Mildner, B.; Bokulić, A.; Situm, K.; Perović, D.; Glojnarić, I.; Parnham, M.J. Enhancement by PL 14736 of granulation and collagen organization in healing wounds and the potential role of egr-1 expression. Eur. J. Pharmacol. 2007, 570, 212–221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, T.; Zhang, K.; Sun, L.; Xue, X.; Zhang, C.; Shu, Z.; Mu, N.; Gu, J.; Zhang, W.; Wang, Y.; et al. Body protective compound-157 enhances alkali-burn wound healing in vivo and promotes proliferation, migration, and angiogenesis in vitro. Drug Des. Devel. Ther. 2015, 9, 2485–2499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikirić, P.; Seiwerth, S.; Grabarević, Z.; Rucman, R.; Petek, M.; Jagić, V.; Turković, B.; Rotkvić, I.; Miše, S.; Zoričić, I.; et al. The influence of a novel pentadecapeptide, BPC 157, on N(G)-nitro-L-arginine methyl ester- and L-arginine-induced effects on stomach mucosa integrity and blood pressure. Eur. J. Pharmacol. 1997, 332, 23–33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Turković, B.; Sikirić, P.; Seiwerth, S.; Miše, S.; Aničić, T.; Petek, M. Stable gastric pentadecapeptide BPC 157 studied for inflammatory bowel disease (PLD-116, PL-14736, Pliva) induces nitric oxide synthesis. Gastroenterology 2004, 126, 287. [Google Scholar]
- Sikiric, P.; Drmic, D.; Boban Blagaic, A.; Tvrdeic, A.; Krezic, I.; Gojkovic, S.; Zizek, H.; Sikiric, S.; Strbe, S.; Smoday, I.M.; et al. Stable gastric pentadecapeptide BPC 157 and the nitric oxide system. In Nitric Oxide: From Research to Therapeutics; Advances in Biochemistry in Health and Disease; Ray, A., Gulati, K., Eds.; Springer Nature: Cham, Switzerland, 2023; Volume 22, pp. 349–375. [Google Scholar] [CrossRef] [Scilit]
- Ruenzi, M.; Stolte, M.; Veljaca, M.; Oreskovic, K.; Peterson, J. Ulcerative Colitis Study Group. A multicenter, randomized, double blind, placebo-controlled phase II study of PL 14736 enema in the treatment of mild-to-moderate ulcerative colitis. Gastroenterology 2005, 128, A584. [Google Scholar]
- Veljaca, M.; Pavic-Sladoljev, D.; Mildner, B.; Brajsa, K.; Bubenik, M.; Stipanicic, S.; Parnham, M. Safety, tolerability and pharmacokinetics of PL14736, a novel agent for treatment of ulcerative colitis, in healthy male volunteers. Gut 2003, 51, A309. [Google Scholar]
- Lee, E.; Padgett, B. Intra-articular injection of BPC 157 for multiple types of knee pain. Altern. Ther. Health Med. 2021, 27, 8–13. [Google Scholar] [PubMed]
- Lee, E.; Walker, C.; Ayadi, B. Effect of BPC-157 on symptoms in patients with interstitial cystitis: A pilot study. Altern. Ther. Health Med. 2024, 30, 12–17. [Google Scholar] [PubMed]
- He, L.; Feng, D.; Guo, H.; Zhou, Y.; Li, Z.; Zhang, K.; Zhang, W.; Wang, S.; Wang, Z.; Hao, Q.; et al. Pharmacokinetics, distribution, metabolism, and excretion of body-protective compound 157, a potential drug for treating various wounds, in rats and dogs. Front. Pharmacol. 2022, 13, 1026182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, C.; Sun, L.; Ren, F.; Huang, P.; Tian, Z.; Cui, J.; Zhang, W.; Wang, S.; Zhang, K.; He, L.; et al. Preclinical safety evaluation of body protective compound-157, a potential drug for treating various wounds. Regul. Toxicol. Pharmacol. 2020, 114, 104665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, E.; Burgess, K. Safety of intravenous infusion of BPC157 in humans: A pilot study. Altern. Ther. Health Med. 2025, 31, 20–24. [Google Scholar] [PubMed]
- October 29, 2024: Meeting of the Pharmacy Compounding Advisory Committee. 2024. Available online: https://www.fda.gov/advisory-committees/advisory-committee-calendar/october-29-2024-meeting-pharmacy-compounding-advisory-committee-10292024 (accessed on 18 March 2025).
- Updated Meeting Time and Public Participation Information. December 4, 2024: Meeting of the Pharmacy Compounding Advisory Committee. 2024. Available online: https://www.fda.gov/advisory-committees/advisory-committee-calendar/updated-meeting-time-and-public-participation-information-december-4-2024-meeting-pharmacy (accessed on 18 March 2025).
- Hrelec, M.; Klicek, R.; Brcic, L.; Brcic, I.; Cvjetko, I.; Seiwerth, S.; Sikiric, P. Abdominal aorta anastomosis in rats and stable gastric pentadecapeptide BPC 157, prophylaxis and therapy. J. Physiol. Pharmacol. 2009, 60, 161–165. [Google Scholar] [PubMed]
- Stupnisek, M.; Franjic, S.; Drmic, D.; Hrelec, M.; Kolenc, D.; Radic, B.; Bojic, D.; Vcev, A.; Seiwerth, S.; Sikiric, P. Pentadecapeptide BPC 157 reduces bleeding time and thrombocytopenia after amputation in rats treated with heparin, warfarin or aspirin. Thromb. Res. 2012, 129, 652–659. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stupnisek, M.; Kokot, A.; Drmic, D.; Hrelec Patrlj, M.; Zenko Sever, A.; Kolenc, D.; Radic, B.; Suran, J.; Bojic, D.; Vcev, A.; et al. Pentadecapeptide BPC 157 reduces bleeding and thrombocytopenia after amputation in rats treated with heparin, warfarin, L-NAME and L-arginine. PLoS ONE 2015, 10, e0123454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Konosic, S.; Petricevic, M.; Ivancan, V.; Konosic, L.; Goluza, E.; Krtalic, B.; Drmic, D.; Stupnisek, M.; Seiwerth, S.; Sikiric, P. Intragastric application of aspirin, clopidogrel, cilostazol, and BPC 157 in rats: Platelet aggregation and blood clot. Oxid. Med. Cell. Longev. 2019, 2019, 9084643. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kolovrat, M.; Gojković, S.; Krezić, I.; Malekinušić, D.; Vrdoljak, B.; Kašnik Kovač, K.; Kralj, T.; Drmić, D.; Barišić, I.; Horvat Pavlov, K.; et al. Pentadecapeptide BPC 157 resolves Pringle maneuver in rats, both ischemia and reperfusion. World J. Hepatol. 2020, 12, 184–206. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gojković, S.; Krezić, I.; Vrdoljak, B.; Malekinušić, D.; Barišić, I.; Petrović, A.; Horvat Pavlov, K.; Kolovrat, M.; Duzel, A.; Knežević, M.; et al. Pentadecapeptide BPC 157 resolves suprahepatic occlusion of the inferior caval vein, Budd–Chiari syndrome model in rats. World J. Gastrointest. Pathophysiol. 2020, 11, 1–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vukojevic, J.; Siroglavic, M.; Kasnik, K.; Kralj, T.; Stancic, D.; Kokot, A.; Kolaric, D.; Drmic, D.; Zenko Sever, A.; Barisic, I.; et al. Rat inferior caval vein (ICV) ligature and particular new insights with the stable gastric pentadecapeptide BPC 157. Vascul. Pharmacol. 2018, 106, 54–66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knezevic, M.; Gojkovic, S.; Krezic, I.; Zizek, H.; Vranes, H.; Malekinusic, D.; Vrdoljak, B.; Knezevic, T.; Horvat Pavlov, K.; Drmic, D.; et al. Complex syndrome of the complete occlusion of the end of the superior mesenteric vein, opposed with the stable gastric pentadecapeptide BPC 157 in rats. Biomedicines 2021, 9, 1029. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Knezevic, M.; Gojkovic, S.; Krezic, I.; Zizek, H.; Malekinusic, D.; Vrdoljak, B.; Knezevic, T.; Vranes, H.; Drmic, D.; Staroveski, M.; et al. Occluded superior mesenteric artery and vein. Therapy with the stable gastric pentadecapeptide BPC 157. Biomedicines 2021, 9, 792. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Knezevic, M.; Gojkovic, S.; Krezic, I.; Zizek, H.; Malekinusic, D.; Vrdoljak, B.; Vranes, H.; Knezevic, T.; Barisic, I.; Horvat Pavlov, K.; et al. Occlusion of the superior mesenteric artery in rats reversed by collateral pathways activation: Gastric pentadecapeptide BPC 157 therapy counteracts multiple organ dysfunction syndrome; intracranial, portal, and caval hypertension; and aortal hypotension. Biomedicines 2021, 9, 609. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Gojkovic, S.; Krezic, I.; Vranes, H.; Zizek, H.; Drmic, D.; Horvat Pavlov, K.; Petrovic, A.; Batelja Vuletic, L.; Milavic, M.; Sikiric, S.; et al. BPC 157 therapy and the permanent occlusion of the superior sagittal sinus in rat: Vascular recruitment. Biomedicines 2021, 9, 744. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Tepes, M.; Gojkovic, S.; Krezic, I.; Zizek, H.; Vranes, H.; Madzar, Z.; Santak, G.; Batelja, L.; Milavic, M.; Sikiric, S.; et al. Stable gastric pentadecapeptide BPC 157 therapy for primary abdominal compartment syndrome in rats. Front. Pharmacol. 2021, 12, 718147. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Tepes, M.; Krezic, I.; Vranes, H.; Smoday, I.M.; Kalogjera, L.; Zizek, H.; Vukovic, V.; Oroz, K.; Kasnik Kovac, K.; Madzar, Z.; et al. Stable gastric pentadecapeptide BPC 157 therapy: Effect on reperfusion following maintained intra-abdominal hypertension (grade III and IV) in rats. Pharmaceuticals 2023, 16, 1554. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Smoday, I.M.; Petrovic, I.; Kalogjera, L.; Vranes, H.; Zizek, H.; Krezic, I.; Gojkovic, S.; Skorak, I.; Hriberski, K.; Brizic, I.; et al. Therapy effect of the stable gastric pentadecapeptide BPC 157 on acute pancreatitis as vascular failure-induced severe peripheral and central syndrome in rats. Biomedicines 2022, 10, 1299. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Kalogjera, L.; Krezic, I.; Smoday, I.M.; Vranes, H.; Zizek, H.; Yago, H.; Oroz, K.; Vukovic, V.; Kavelj, I.; Novosel, L.; et al. Stomach perforation-induced general occlusion/occlusion-like syndrome and stable gastric pentadecapeptide BPC 157 therapy effect. World J. Gastroenterol. 2023, 29, 4289–4316. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Strbe, S.; Gojkovic, S.; Krezic, I.; Zizek, H.; Vranes, H.; Barisic, I.; Strinic, D.; Orct, T.; Vukojevic, J.; Ilic, S.; et al. Over-dose lithium toxicity as an occlusive-like syndrome in rats and gastric pentadecapeptide BPC 157. Biomedicines 2021, 9, 1506. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strbe, S.; Smoday, I.M.; Krezic, I.; Kalogjera, L.; Vukovic, V.; Zizek, H.; Gojkovic, S.; Vranes, H.; Barisic, I.; Sikiric, S.; et al. Innate vascular failure by application of neuroleptics, amphetamine, and domperidone rapidly induced severe occlusion/occlusion-like syndromes in rats and stable gastric pentadecapeptide BPC 157 as therapy. Pharmaceuticals 2023, 16, 788. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Premuzic Mestrovic, I.; Smoday, I.M.; Kalogjera, L.; Krezic, I.; Zizek, H.; Vranes, H.; Vukovic, V.; Oroz, K.; Skorak, I.; Brizic, I.; et al. Antiarrhythmic sotalol, occlusion/occlusion-like syndrome in rats, and stable gastric pentadecapeptide BPC 157 therapy. Pharmaceuticals 2023, 16, 977. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Barisic, I.; Balenovic, D.; Udovicic, M.; Bardak, D.; Strinic, D.; Vlainić, J.; Vranes, H.; Smoday, I.M.; Krezic, I.; Milavic, M.; et al. Stable gastric pentadecapeptide BPC 157 may counteract myocardial infarction induced by isoprenaline in rats. Biomedicines 2022, 10, 265. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Smoday, I.M.; Krezic, I.; Kalogjera, L.; Vukovic, V.; Zizek, H.; Skoro, M.; Kasnik Kovac, K.; Vranes, H.; Barisic, I.; Sikiric, S.; et al. Pentadecapeptide BPC 157 as therapy for inferior caval vein embolization: Recovery of sodium laurate-post-embolization syndrome in rats. Pharmaceuticals 2023, 16, 1507. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Gojkovic, S.; Krezic, I.; Vranes, H.; Zizek, H.; Drmic, D.; Batelja Vuletic, L.; Milavic, M.; Sikiric, S.; Stilinovic, I.; Simeon, P.; et al. Robert’s intragastric alcohol-induced gastric lesion model as an escalated general peripheral and central syndrome, counteracted by the stable gastric pentadecapeptide BPC 157. Biomedicines 2021, 9, 1300. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Sikiric, P.; Seiwerth, S.; Rucman, R.; Turkovic, B.; Rokotov, D.S.; Brcic, L.; Sever, M.; Klicek, R.; Radic, B.; Drmic, D.; et al. Toxicity by NSAIDs. Counteraction by stable gastric pentadecapeptide BPC 157. Curr. Pharm. Des. 2013, 19, 76–83. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Atzemian, N.; Kareli, D.; Ragia, G.; Manolopoulos, V.G. Distinct pleiotropic effects of direct oral anticoagulants on cultured endothelial cells: A comprehensive review. Front. Pharmacol. 2023, 14, 1244098. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Alfano, F.; Gori, A.M.; Berteotti, M.; Rogolino, A.; Cesari, F.; Salvadori, E.; Formelli, B.; Pescini, F.; Barbato, C.; Giusti, B.; et al. Pleiotropic effects of oral anticoagulant therapy: Is there a difference between VKAs and DOACs? Biomedicines 2025, 13, 1850. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Puech, C.; Delavenne, X.; He, Z.; Forest, V.; Mismetti, P.; Perek, N. Direct oral anticoagulants are associated with limited damage of endothelial cells of the blood-brain barrier mediated by the thrombin/PAR-1 pathway. Brain Res. 2019, 1719, 57–63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gikakis, N.; Khan, M.M.; Hiramatsu, Y.; Gorman, J.H., 3rd; Hack, C.E.; Sun, L.; Rao, A.K.; Niewiarowski, S.; Colman, R.W.; Edmunds, L.H., Jr. Effect of factor Xa inhibitors on thrombin formation and complement and neutrophil activation during in vitro extracorporeal circulation. Circulation 1996, 94, II341–II346. [Google Scholar] [PubMed]
- Ten Cate, H.; Guzik, T.J.; Eikelboom, J.; Spronk, H.M.H. Pleiotropic actions of factor Xa inhibition in cardiovascular prevention: Mechanistic insights and implications for anti-thrombotic treatment. Cardiovasc. Res. 2021, 117, 2030–2044. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Bal Dit Sollier, C.; Dillinger, J.-G.; Drouet, L. Anticoagulant activity and pleiotropic effects of heparin. J. Med. Vasc. 2020, 45, 147–157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Price, P.A.; Faus, S.A.; Williamson, M.K. Warfarin causes rapid calcification of the elastic lamellae in rat arteries and heart valves. Arterioscler. Thromb. Vasc. Biol. 1998, 18, 1400–1407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schurgers, L.J.; Spronk, H.M.H.; Skepper, J.N.; Hackeng, T.M.; Shanahan, C.M.; Vermeer, C.; Weissberg, P.L.; Proudfoot, D. Post-translational modifications regulate matrix Gla protein function: Importance for inhibition of vascular smooth muscle cell calcification. J. Thromb. Haemost. 2007, 5, 2503–2511. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, X.; Pu, D.; Wang, R.; Zhang, J.; Lin, Y.; Wang, Y.; Zhai, N.; Peng, X.; Zhou, Q.; Li, L. Gas6/AXL pathway: Immunological landscape and therapeutic potential. Front. Oncol. 2023, 13, 1121130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fraineau, S.; Monvoisin, A.; Clarhaut, J.; Talbot, J.; Simonneau, C.; Kanthou, C.; Kanse, S.M.; Philippe, M.; Benzakour, O. The vitamin K–dependent anticoagulant factor, protein S, inhibits multiple VEGF-A–induced angiogenesis events in a Mer- and SHP2-dependent manner. Blood 2012, 120, 5073–5083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barrett, H.; O’Keeffe, M.; Kavanagh, E.; Walsh, M.; O’Connor, E.M. Is matrix Gla protein associated with vascular calcification? A systematic review. Nutrients 2018, 10, 415. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- de Vries, F.; Bittner, R.; Maresz, K.; Machuron, F.; Gåserød, O.; Jeanne, J.-F.; Schurgers, L.J. Effects of one-year menaquinone-7 supplementation on vascular stiffness and blood pressure in post-menopausal women. Nutrients 2025, 17, 815. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, W.Y.-H.; Bhutani, T.; Kornik, R. Warfarin-associated nonuremic calciphylaxis. JAMA Dermatol. 2017, 153, 309–314. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Patrono, C.; Coller, B.; FitzGerald, G.A.; Hirsh, J.; Roth, G. Platelet-active drugs: The relationships among dose, effectiveness, and side effects: The Seventh ACCP Conference on Antithrombotic and Thrombolytic Therapy. Chest 2004, 126, 234S–264S. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vilahur, G.; Fuster, V. Interplay between platelets and coagulation: From protective haemostasis to pathological arterial thrombosis. Eur. Heart J. 2025, 46, 413–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davì, G.; Patrono, C. Platelet activation and atherothrombosis. N. Engl. J. Med. 2007, 357, 2482–2494. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grosser, N.; Schröder, H. Aspirin protects endothelial cells from oxidant damage via the nitric oxide-cGMP pathway. Arterioscler. Thromb. Vasc. Biol. 2003, 23, 1345–1351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, X.; Zhang, G.; Cao, X. The function and regulation of platelet P2Y12 receptor. Cardiovasc. Drugs Ther. 2023, 37, 199–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gao, Y.; Yu, C.; Pi, S.; Mao, L.; Hu, B. The role of P2Y12 receptor in ischemic stroke of atherosclerotic origin. Cell. Mol. Life Sci. 2019, 76, 341–354. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Didehvar, K.; Haghshenas, M.; Yarmohammadi, R.; Hajikarimloo, B.; Ghafoury, R. Tissue plasminogen activator as an approved strategy for ischemic stroke: A review of tPA’s structure, mechanism of action and the novel targeting methods. J. Mol. Neurosci. 2025, 75, 152. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Zhu, J.; Wan, Y.; Xu, H.; Wu, Y.; Hu, B.; Jin, H. The role of endogenous tissue-type plasminogen activator in neuronal survival after ischemic stroke: Friend or foe? Cell. Mol. Life Sci. 2019, 76, 1489–1506. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Zhao, M.; Wang, J.; Liu, G.; Li, S.; Ding, Y.; Ji, X.; Zhao, W. Multi-target and multi-phase adjunctive cerebral protection for acute ischemic stroke in the reperfusion era. Biomolecules 2024, 14, 1181. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Yang, Y.; Guo, D.; Liu, Y.; Li, Y. Advances in neuroprotective therapy for acute ischemic stroke. Explor. Neuroprot. Ther. 2024, 4, 55–71. [Google Scholar] [CrossRef] [Scilit]
- Kennedy, J.W. Thrombolytic therapy in acute myocardial infarction. J. Am. Coll. Cardiol. 1999, 33, 1829–1832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patriarcheas, V.; Pikoulas, A.; Kostis, M.; Charpidou, A.; Dimakakos, E. Heparin-induced thrombocytopenia: Pathophysiology, diagnosis and management. Cureus 2020, 12, e7385. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Comp, P.C.; Elrod, J.P.; Karzenski, S. Warfarin-induced skin necrosis. Semin. Thromb. Hemost. 1990, 16, 293–298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Osman, R.M.; Suliman, A.; Mohamedosman, R.; Tahameed, T.; Mohamed, E. Warfarin-induced skin necrosis: A narrative review of clinical features, risk factors, and treatment strategies. Ann. Med. Surg. 2025, 87, 7249–7260. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Grip, L.; Blombäck, M.; Schulman, S. Hypercoagulable state and thromboembolism following warfarin withdrawal in post-myocardial-infarction patients. Eur. Heart J. 1991, 12, 1225–1233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Junqueira, D.R.; Zorzela, L.M.; Perini, E. Unfractionated heparin versus low molecular weight heparins for avoiding heparin-induced thrombocytopenia in postoperative patients. Cochrane Database Syst. Rev. 2017, 4, CD007557. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Chen, L.-Y.; Khan, N.; Lindenbauer, A.; Nguyen, T.-H. When will fondaparinux induce thrombocytopenia? Bioconjug Chem. 2022, 33, 1574–1583. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Krauel, K.; Fürll, B.; Warkentin, T.E.; Weitschies, W.; Kohlmann, T.; Sheppard, J.I.; Greinacher, A. Heparin-induced thrombocytopenia—Therapeutic concentrations of danaparoid, unlike fondaparinux and direct thrombin inhibitors, inhibit formation of platelet factor 4-heparin complexes. J. Thromb. Haemost. 2008, 6, 2160–2167. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smythe, M.A.; Priziola, J.; Dobesh, P.P.; Wirth, D.; Cuker, A.; Wittkowsky, A.K. Guidance for the practical management of the heparin anticoagulants in the treatment of venous thromboembolism. J. Thromb. Thrombolysis 2016, 41, 165–186. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Wigle, P.; Hein, B.; Bloomfield, H.E.; Tubb, M.; Doherty, M. Updated guidelines on outpatient anticoagulation. Am. Fam. Physician 2013, 87, 556–566. [Google Scholar] [PubMed]
- Pollack, C.V.; Reilly, P.A.; Eikelboom, J.; Glund, S.; Verhamme, P.; Bernstein, R.A.; Dubiel, R.; Huisman, M.V.; Hylek, E.M.; Kamphuisen, P.W.; et al. Idarucizumab for dabigatran reversal. N. Engl. J. Med. 2015, 373, 511–520. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pollack, C.V.; Reilly, P.A.; van Ryn, J.; Eikelboom, J.W.; Glund, S.; Bernstein, R.A.; Dubiel, R.; Huisman, M.V.; Hylek, E.M.; Kam, C.-W.; et al. Idarucizumab for dabigatran reversal: Full cohort analysis. N. Engl. J. Med. 2017, 377, 431–441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chandiramani, A.S.; Jenkin, I.; Botezatu, B.; Harky, A. Protamine-induced coronary graft thrombosis: A review. J. Cardiothorac. Vasc. Anesth. 2022, 36, 2679–2684. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boer, C.; Meesters, M.I.; Veerhoek, D.; Vonk, A.B.A. Anticoagulant and side-effects of protamine in cardiac surgery: A narrative review. Br. J. Anaesth. 2018, 120, 914–927. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alrayes, H.; Alsaadi, A.; Alkhatib, A.; Patel, D.A.; Alqarqaz, M.; Frisoli, T.; Fuller, B.; Khandelwal, A.; Koenig, G.; O’Neill, B.P.; et al. Safety and complications associated with the use of protamine in percutaneous coronary intervention. J. Invasive Cardiol. 2025, 37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharifi-Rad, J.; Sharopov, F.; Ezzat, S.M.; Zam, W.; Ademiluyi, A.O.; Oyeniran, O.H.; Adetunji, C.O.; Roli, O.I.; Živković, J.; Martorell, M.; et al. An updated review on glycoprotein IIb/IIIa inhibitors as antiplatelet agents: Basic and clinical perspectives. High Blood Press. Cardiovasc. Prev. 2023, 30, 93–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hasan, N.; Jauregui, W.; Zubair, M.; Pushparajan, V.K.; Carson, B.J.; Attaluri, D.M.; Dixon, D.; Jaisinghani, A.; Chuecos, A.; Ravichandran, D.; et al. Adverse drug effect profiles of Gp2b/3a inhibitors: A comparative review of the last two decades. Cureus 2023, 15, e49332. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Guo, Y.-L.; Li, J.-J.; Yuan, J.-Q.; Qin, X.-W.; Zheng, X.; Mu, C.-W.; Hua, Y.-H. Profound thrombocytopenia induced by clopidogrel with a prior history of long-term safe administration. World J. Cardiol. 2010, 2, 160–162. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Frydrych, M.; Janeczek, M.; Małyszek, A.; Nelke, K.; Dobrzyński, M.; Lukaszewski, M. Prothrombotic rebound after discontinuation of direct oral anticoagulants therapy: A systematic review. J. Clin. Med. 2024, 13, 6606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burger, W.; Chemnitius, J.-M.; Kneissl, G.D.; Rücker, G. Low-dose aspirin for secondary cardiovascular prevention—Cardiovascular risks after its perioperative withdrawal versus bleeding risks with its continuation—Review and meta-analysis. J. Intern. Med. 2005, 257, 399–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verstraete, M. Third-generation thrombolytic drugs. Am. J. Med. 2000, 109, 52–58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Collen, D.; Lijnen, H.R. Basic and clinical aspects of fibrinolysis and thrombolysis. Blood 1991, 78, 3114–3124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gold, H.K.; Leinbach, R.C.; Garabedian, H.D.; Yasuda, T.; Johns, J.A.; Grossbard, E.B.; Palacios, I.; Collen, D. Acute coronary reocclusion after thrombolysis with recombinant human tissue-type plasminogen activator: Prevention by a maintenance infusion. Circulation 1986, 73, 347–352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoffmeister, H.M.; Szabo, S.; Helber, U.; Seipel, L. The thrombolytic paradox. Thromb. Res. 2001, 103, S51–S55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Napolitano, F.; Montuori, N. Role of plasminogen activation system in platelet pathophysiology: Emerging concepts for translational applications. Int. J. Mol. Sci. 2022, 23, 6065. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taylor, F.B., Jr.; Toh, C.H.; Hoots, W.K.; Wada, H.; Levi, M. Scientific Subcommittee on Disseminated Intravascular Coagulation (DIC) of the International Society on Thrombosis and Haemostasis (ISTH). Towards definition, clinical and laboratory criteria, and a scoring system for disseminated intravascular coagulation. Thromb. Haemost. 2001, 86, 1327–1330. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Totoki, T.; Koami, H.; Makino, Y.; Wada, T.; Ito, T.; Yamakawa, K.; Iba, T. Heparin therapy in sepsis and sepsis-associated disseminated intravascular coagulation: A systematic review and meta-analysis. Thromb. J. 2024, 22, 84. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Rock, G.A.; Shumak, K.H.; Buskard, N.A.; Blanchette, V.S.; Kelton, J.G.; Nair, R.C.; Spasoff, R.A. Canadian Apheresis Study Group. Comparison of plasma exchange with plasma infusion in the treatment of thrombotic thrombocytopenic purpura. N. Engl. J. Med. 1991, 325, 393–397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Legendre, C.M.; Licht, C.; Muus, P.; Greenbaum, L.A.; Babu, S.; Bedrosian, C.; Bingham, C.; Cohen, D.J.; Delmas, Y.; Douglas, K.; et al. Terminal complement inhibitor eculizumab in atypical hemolytic-uremic syndrome. N. Engl. J. Med. 2013, 368, 2169–2181. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Licht, C.; Greenbaum, L.A.; Muus, P.; Babu, S.; Bedrosian, C.L.; Cohen, D.J.; Delmas, Y.; Douglas, K.; Furman, R.R.; Gaber, O.A.; et al. Efficacy and safety of eculizumab in atypical hemolytic uremic syndrome from 2-year extensions of phase 2 studies. Kidney Int. 2015, 87, 1061–1073. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Drmic, D.; Samara, M.; Vidovic, T.; Malekinusic, D.; Antunovic, M.; Vrdoljak, B.; Ruzman, J.; Milkovic Perisa, M.; Horvat Pavlov, K.; Jeyakumar, J.; et al. Counteraction of perforated cecum lesions in rats: Effects of pentadecapeptide BPC 157, L-NAME and L-arginine. World J. Gastroenterol. 2018, 24, 5462–5476. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Singer, A.J.; Clark, R.A.F. Cutaneous wound healing. N. Engl. J. Med. 1999, 341, 738–746. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruggeri, Z.M. Old concepts and new developments in the study of platelet aggregation. J. Clin. Investig. 2000, 105, 699–701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seiwerth, S.; Milavic, M.; Vukojevic, J.; Gojkovic, S.; Krezic, I.; Vuletic, L.B.; Pavlov, K.H.; Petrovic, A.; Sikiric, S.; Vranes, H.; et al. Stable gastric pentadecapeptide BPC 157 and wound healing. Front. Pharmacol. 2021, 12, 627533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Seiwerth, S.; Grabarevic, Z.; Petek, M.; Rucman, R.; Turkovic, B.; Rotkvic, I.; Jagic, V.; Duvnjak, M.; Mise, S.; et al. The beneficial effect of BPC 157, a 15 amino acid peptide BPC fragment, on gastric and duodenal lesions induced by restraint stress, cysteamine and 96% ethanol in rats: A comparative study with H2 receptor antagonists, dopamine promotors and gut peptides. Life Sci. 1994, 54, PL63–PL68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Q.; Liu, C.; An, J.; Liu, J.; Wang, Y.; Cai, Y. Mechanisms of microbial infection and wound healing in diabetic foot ulcer: Pathogenicity in the inflammatory-proliferative phase, chronicity, and treatment strategies. Front. Endocrinol. 2025, 16, 1657928. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seveljević-Jaran, D.; Cuzić, S.; Dominis-Kramarić, M.; Glojnarić, I.; Ivetić, V.; Radosević, S.; Parnham, M.J. Accelerated healing of excisional skin wounds by PL 14736 in alloxan-hyperglycemic rats. Ski. Pharmacol. Physiol. 2006, 19, 266–274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mikus, D.; Sikiric, P.; Seiwerth, S.; Petricevic, A.; Aralica, G.; Druzijancic, N.; Rucman, R.; Petek, M.; Pigac, B.; Perovic, D.; et al. Pentadecapeptide BPC 157 cream improves burn-wound healing and attenuates burn-gastric lesions in mice. Burns 2001, 27, 817–827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Seiwerth, S.; Mise, S.; Staresinic, M.; Bedekovic, V.; Zarkovic, N.; Borovic, S.; Gjurasin, M.; Boban-Blagaic, A.; Batelja, L.; et al. Corticosteroid-impairment of healing and gastric pentadecapeptide BPC-157 creams in burned mice. Burns 2003, 29, 323–334. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bilic, M.; Bumber, Z.; Blagaic, A.B.; Batelja, L.; Seiwerth, S.; Sikiric, P. The stable gastric pentadecapeptide BPC 157, given locally, improves CO2 laser healing in mice. Burns 2005, 31, 310–315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seiwerth, S.; Sikiric, P.; Grabarevic, Z.; Zoricic, I.; Hanzevacki, M.; Ljubanovic, D.; Coric, V.; Konjevoda, P.; Petek, M.; Rucman, R.; et al. BPC 157’s effect on healing. J. Physiol. Paris 1997, 91, 173–178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Krivic, A.; Anic, T.; Seiwerth, S.; Huljev, D.; Sikiric, P. Achilles detachment in rat and stable gastric pentadecapeptide BPC 157: Promoted tendon-to-bone healing and opposed corticosteroid aggravation. J. Orthop. Res. 2006, 24, 982–989. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Krivic, A.; Majerovic, M.; Jelic, I.; Seiwerth, S.; Sikiric, P. Modulation of early functional recovery of Achilles tendon to bone unit after transection by BPC 157 and methylprednisolone. Inflamm. Res. 2008, 57, 205–210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Staresinic, M.; Sebecic, B.; Patrlj, L.; Jadrijevic, S.; Suknaic, S.; Perovic, D.; Aralica, G.; Zarkovic, N.; Borovic, S.; Srdjak, M.; et al. Gastric pentadecapeptide BPC 157 accelerates healing of transected rat Achilles tendon and in vitro stimulates tendocytes growth. J. Orthop. Res. 2003, 21, 976–983. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brcic, L.; Brcic, I.; Staresinic, M.; Novinscak, T.; Sikiric, P.; Seiwerth, S. Modulatory effect of gastric pentadecapeptide BPC 157 on angiogenesis in muscle and tendon healing. J. Physiol. Pharmacol. 2009, 60, 191–196. [Google Scholar] [PubMed]
- Sikiric, P.; Buljan, M.; Vnuk, D.; Krstonijevic, Z.; Sever, M.; Lojo, N.; Drmic, D.; Zenko Sever, A.; Baric, M.; Starcevic, N.; et al. Effect of pentadecapeptide BPC 157 on rotator cuff tear injury in rat. FASEB J. 2014, 28, 844.9. [Google Scholar] [CrossRef] [Scilit]
- Jukic, I.; Kokic, N.; Sikiric, P.; Mise, S.; Seiwerth, S.; Anic, T.; Jukic, J. Gastric pentadecapeptide BPC 157 heals myofibrotic contracture induced by multiple blunt leg injury in the rat. Dig. Dis. Sci. 2003, 48, 1874. [Google Scholar]
- Cerovecki, T.; Bojanic, I.; Brcic, L.; Radic, B.; Vukoja, I.; Seiwerth, S.; Sikiric, P. Pentadecapeptide BPC 157 (PL 14736) improves ligament healing in the rat. J. Orthop. Res. 2010, 28, 1155–1161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Staresinic, M.; Petrovic, I.; Novinscak, T.; Jukic, I.; Pevec, D.; Suknaic, S.; Kokic, N.; Brcic, L.; Seiwerth, S.; Sikiric, P.; et al. Effective therapy of transected quadriceps muscle in rat: Gastric pentadecapeptide BPC 157. J. Orthop. Res. 2006, 24, 1109–1117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Novinscak, T.; Brcic, L.; Staresinic, M.; Jukic, I.; Radic, B.; Pevec, D.; Mise, S.; Tomasovic, S.; Brcic, I.; Banic, T.; et al. Gastric pentadecapeptide BPC 157 as an effective therapy for muscle crush injury in the rat. Surg. Today 2008, 38, 716–725. [Google Scholar] [CrossRef] [Scilit]
- Pevec, D.; Novinscak, T.; Brcic, L.; Sipos, K.; Jukic, I.; Staresinic, M.; Mise, S.; Brcic, I.; Kolenc, D.; Klicek, R.; et al. Impact of pentadecapeptide BPC 157 on muscle healing impaired by systemic corticosteroid application. Med. Sci. Monit. 2010, 16, BR81–BR88. [Google Scholar] [PubMed]
- Mihovil, I.; Radic, B.; Brcic, L.; Brcic, I.; Vukoja, I.; Ilic, S.; Boban Blagaic, A.; Seiwerth, S.; Sikiric, P. Beneficial effect of pentadecapeptide BPC 157 on denervated muscle in rats. J. Physiol. Pharmacol. 2009, 60, 69. [Google Scholar]
- Japjec, M.; Horvat Pavlov, K.; Petrovic, A.; Staresinic, M.; Sebecic, B.; Buljan, M.; Vranes, H.; Giljanovic, A.; Drmic, D.; Japjec, M.; et al. Stable gastric pentadecapeptide BPC 157 as a therapy for the disable myotendinous junctions in rats. Biomedicines 2021, 9, 1547. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matek, D.; Matek, I.; Staresinic, E.; Japjec, M.; Bojanic, I.; Boban Blagaic, A.; Beketic Oreskovic, L.; Oreskovic, I.; Ziger, T.; Novinscak, T.; et al. Stable gastric pentadecapeptide BPC 157 as therapy after surgical detachment of the quadriceps muscle from its attachments for muscle-to-bone reattachment in rats. Pharmaceutics 2025, 17, 119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Masnec, S.; Kokot, A.; Zlatar, M.; Kalauz, M.; Kunjko, K.; Radic, B.; Klicek, R.; Drmic, D.; Lazic, R.; Brcic, L.; et al. Perforating corneal injury in rat and pentadecapeptide BPC 157. Exp. Eye Res. 2015, 136, 9–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bajramagic, S.; Sever, M.; Rasic, F.; Staresinic, M.; Skrtic, A.; Beketic Oreskovic, L.; Oreskovic, I.; Strbe, S.; Loga Zec, S.; Hrabar, J.; et al. Stable gastric pentadecapeptide BPC 157 and intestinal anastomoses therapy in rats—A review. Pharmaceuticals 2024, 17, 1081. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Sikiric, P.; Drmic, D.; Sever, M.; Klicek, R.; Blagaic, A.B.; Tvrdeic, A.; Kralj, T.; Kovac, K.K.; Vukojevic, J.; Siroglavic, M.; et al. Fistulas healing: Stable gastric pentadecapeptide BPC 157 therapy. Curr. Pharm. Des. 2020, 26, 2991–3000. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Skorjanec, S.; Dolovski, Z.; Kocman, I.; Brcic, L.; Blagaic Boban, A.; Batelja, L.; Coric, M.; Sever, M.; Klicek, R.; Berkopic, L.; et al. Stable gastric pentadecapeptide BPC 157 heals rat colovesical fistula: Therapy for unhealed gastrocutaneous fistulas in rats as a model for analogous healing of persistent skin wounds and persistent gastric ulcers. Dig. Dis. Sci. 2009, 54, 46–56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Klicek, R.; Sever, M.; Radic, B.; Drmic, D.; Kocman, I.; Zoricic, I.; Vuksic, T.; Ivica, M.; Barisic, I.; Ilic, S.; et al. Pentadecapeptide BPC 157, in clinical trials as a therapy for inflammatory bowel disease (PL14736), is effective in the healing of colocutaneous fistulas in rats: Role of the nitric oxide-system. J. Pharmacol. Sci. 2008, 108, 7–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Skorjanec, S.; Kokot, A.; Drmic, D.; Radic, B.; Sever, M.; Klicek, R.; Kolenc, D.; Zenko, A.; Lovric Bencic, M.; Belosic Halle, Z.; et al. Duodenocutaneous fistula in rats as a model for “wound healing-therapy”: The effect of pentadecapeptide BPC 157, L-nitro-arginine methyl ester and L-arginine. J. Physiol. Pharmacol. 2015, 66, 581–590. [Google Scholar] [PubMed]
- Cesarec, V.; Becejac, T.; Misic, M.; Djakovic, Z.; Olujic, D.; Drmic, D.; Brcic, L.; Rokotov, D.S.; Seiwerth, S.; Sikiric, P. Pentadecapeptide BPC 157 and esophagocutaneous fistula healing therapy. Eur. J. Pharmacol. 2013, 701, 203–212. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Madzarac, G.; Becejac, T.; Penovic, T.; Drazenovic, D.; Kralj, L.; Popović Dolić, M.; Sikiric, S.; Beketic Oreskovic, L.; Oreskovic, I.; Strbe, S.; et al. Tracheocutaneous fistula resolved by pentadecapeptide BPC 157 therapy through the NO-system—Triple NO-agent approach in rats. Pharmaceuticals 2026, 19, 145. [Google Scholar] [CrossRef] [Scilit]
- Vukusic, D.; Zenko Sever, A.; Sever, M.; Drmic, D.; Milavic, M.; Sikiric, S.; Rasic, D.; Krezic, I.; Gojkovic, S.; Prtoric, A.; et al. Duodenocolic fistula healing by pentadecapeptide BPC 157 in rats: A cytoprotection viewpoint. J. Physiol. Pharmacol. 2024, 75, 89–104. [Google Scholar] [CrossRef] [PubMed]
- Rasic, D.; Zenko Sever, A.; Rasic, F.; Strbe, S.; Rasic, Z.; Djuzel, A.; Duplancic, B.; Boban Blagaic, A.; Skrtic, A.; Seiwerth, S.; et al. Stable gastric pentadecapeptide BPC 157 heals established vesicovaginal fistula and counteracts stone formation in rats. Biomedicines 2021, 9, 1206. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grgic, T.; Grgic, D.; Drmic, D.; Sever, A.Z.; Petrovic, I.; Sucic, M.; Kokot, A.; Klicek, R.; Sever, M.; Seiwerth, S.; et al. Assessment of colovesical fistula healing in rats by pentadecapeptide BPC 157. Eur. J. Pharmacol. 2016, 780, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baric, M.; Sever, A.Z.; Vuletic, L.B.; Rasic, Z.; Sever, M.; Drmic, D.; Pavelic-Turudic, T.; Sucic, M.; Vrcic, H.; Seiwerth, S.; et al. Stable gastric pentadecapeptide BPC 157 heals rectovaginal fistula in rats. Life Sci. 2016, 148, 63–70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rahman, O.F.; Lee, S.J.; Seeds, W.A. Therapeutic peptides in orthopaedics: Applications, challenges, and future directions. J. Am. Acad. Orthop. Surg. Glob. Res. Rev. 2026, 10, e25.00236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mayfield, C.K.; Bolia, I.K.; Feingold, C.L.; Lin, E.H.; Liu, J.N.; Rick Hatch, G.F.; Gamradt, S.C.; Weber, A.E. Injectable peptide therapy: A primer for orthopaedic and sports medicine physicians. Am. J. Sports Med. 2026, 54, 223–229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DeFoor, M.T.; Dekker, T.J. Injectable therapeutic peptides—An adjunct to regenerative medicine and sports performance? Arthroscopy 2025, 41, 150–152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giandonato, J.A.; Tringali, V. Pentadecapeptide BPC 157: Panacea or overhyped peptide? Eur. J. Phys. Educ. Sport Sci. 2025, 12, 1–14. [Google Scholar] [CrossRef] [Scilit]
- McGuire, F.P.; Martinez, R.; Lenz, A.; Skinner, L.; Cushman, D.M. Regeneration or risk? A narrative review of BPC 157 for musculoskeletal healing. Curr. Rev. Musculoskelet. Med. 2025, 18, 611–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dekker, T.J. Editorial commentary: Testosterone, growth hormone, and vitamin D supplementation is not routinely indicated for orthopaedic surgery patients. Arthroscopy 2025, 41, 3151–3152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vasireddi, N.; Hahamyan, H.; Salata, M.J.; Karns, M.; Calcei, J.G.; Voos, J.E.; Apostolakos, J.M. Emerging use of BPC 157 in orthopaedic sports medicine: A systematic review. HSS J. 2025, 21, 485–495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Whitehouse, M. Concerning BPC-157, a natural pentadecapeptide, that acts as a cytoprotectant and is believed to protect the gastro-intestinal tract (GIT). Inflammopharmacology 2025, 33, 4879–4881. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DiStefano, M.J.; Dardouri, M.; Moore, G.D.; Saseen, J.J.; Nair, K.V. Compounded glucagon-like peptide-1 receptor agonists for weight loss: The direct-to-consumer market in Colorado. J. Pharm. Policy Pract. 2025, 18, 2441220. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Chan, M.K.S.; Wong, M.B.F.; Chernykh, V.; Iemeliyanova, M.; Alvin, G.; Nishkumai, O.; Lakey, J.R.T.; Klokol, D. Emerging anabolic and regenerative peptides in athletic body re-composition and bodybuilding: Mechanisms of action, dosing strategies, and evidence review. J. Stem Cell Res. 2025, 6, 1–28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, G.; Fang, W.; Chung, J.; Dunn, E.; Lin, R.; Mo, K.; Bascharon, R.; McGee, R. Application of peptide therapy for ligaments and tendons: A narrative review. J. Orthop. Rep. 2025, 100791. [Google Scholar] [CrossRef] [Scilit]
- Cushman, C.J.; Ibrahim, A.F.; Smith, A.D.; Hernandez, E.J.; MacKay, B.; Zumwalt, M. Local and systemic peptide therapies for soft tissue regeneration: A narrative review. Yale J. Biol. Med. 2024, 97, 399–413. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gwyer, D.; Wragg, N.M.; Wilson, S.L. Gastric pentadecapeptide body protection compound BPC 157 and its role in accelerating musculoskeletal soft tissue healing. Cell Tissue Res. 2019, 377, 153–159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, A.T.; Sneistrup, C.; Berg, T.M. Prostaglandin E1 increases microcirculation in random pattern flaps on rats measured with laser Doppler perfusion imaging. Plast. Reconstr. Surg. Glob. Open 2017, 5, e1202. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Takahashi, S.; Tagami, Y.; Maie, O. Clinical effects of G-511 ointment (prostaglandin E1 ointment) on the treatment of chronic skin ulcers. Rinshouiyaku 1994, 10, 113–125. [Google Scholar]
- Duthois, S.; Cailleux, N.; Benosman, B.; Lévesque, H. Tolerance of iloprost and results of treatment of chronic severe lower limb ischaemia in diabetic patients: A retrospective study of 64 consecutive cases. Diabetes Metab. 2003, 29, 36–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, J.Z.; Maruyama, K.; Iwatsuki, K.; Ono, I.; Kaneko, F. Effect of prostaglandin E1 on human keratinocytes and dermal fibroblasts: A possible mechanism for the healing of skin ulcers. Exp. Dermatol. 1994, 3, 164–170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, E.S.; Atrasz, R.G.; Dickie, E.G.; Aronoff, D.M.; Stambolic, V.; Mak, T.W.; Moore, B.B.; Peters-Golden, M. Prostaglandin E2 inhibits fibroblast migration by E-prostanoid 2 receptor-mediated increase in PTEN activity. Am. J. Respir. Cell Mol. Biol. 2005, 32, 135–141. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Zahedipour, F.; Butler, A.E.; Eid, A.H.; Sahebkar, A. Pleiotropic properties of statins via angiogenesis modulation in cardiovascular disease. Drug Discov. Today 2022, 27, 103325. [Google Scholar] [CrossRef] [Scilit]
- Torgal, S.S.; Hiremath, S.V.; Majagi, S.I.; Gouripur, V.V.; Patil, P.A.; Hogade, A.P. Evaluation of wound healing activity of angiotensin converting enzyme inhibitors in Wistar rats. Recent Res. Sci. Technol. 2010, 2, 76–80. [Google Scholar]
- Fang, Q.-Q.; Wang, X.-F.; Zhao, W.-Y.; Ding, S.-L.; Shi, B.-H.; Xia, Y.; Yang, H.; Wu, L.-H.; Li, C.-Y.; Tan, W.-Q. Angiotensin-converting enzyme inhibitor reduces scar formation by inhibiting both canonical and noncanonical TGF-β1 pathways. Sci. Rep. 2018, 8, 3332. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.D.; Liu, M.; Chen, X.H.; Yang, Z.J. Effect of angiotensin receptor blockers on flow-mediated vasodilation: A meta-analysis of randomized controlled trials. Cardiology 2015, 131, 69–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, S.; Wang, X.; Wang, G.; Wang, X. Mechanism and application of β-adrenoceptor blockers in soft tissue wound healing. Med. Res. Rev. 2024, 44, 422–452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Romana-Souza, B.; Porto, L.C.; Monte-Alto-Costa, A. Cutaneous wound healing of chronically stressed mice is improved through catecholamines blockade. Exp. Dermatol. 2010, 19, 821–829. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ali, A.; Herndon, D.N.; Mamachen, A.; Hasan, S.; Andersen, C.R.; Grogans, R.-J.; Brewer, J.L.; Lee, J.O.; Heffernan, J.; Suman, O.E.; et al. Propranolol attenuates hemorrhage and accelerates wound healing in severely burned adults. Crit. Care 2015, 19, 217. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Assis de Brito, T.L.; Monte-Alto-Costa, A.; Romana-Souza, B. Propranolol impairs the closure of pressure ulcers in mice. Life Sci. 2014, 100, 138–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raut, S.B.; Nerlekar, S.R.; Pawar, S.; Patil, A.N. An evaluation of the effects of nonselective and cardioselective β-blockers on wound healing in Sprague Dawley rats. Indian J. Pharmacol. 2012, 44, 629–633. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Zolfagharnezhad, H.; Khalili, H.; Mohammadi, M.; Niknam, S.; Vatanara, A. Topical nifedipine for the treatment of pressure ulcer: A randomized, placebo-controlled clinical trial. Am. J. Ther. 2021, 28, e41–e51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teimouri, A.; Yeung, P.; Agu, R.U. Drug-release assessment of compounded topical nifedipine and diltiazem in commonly used bases for wound healing. Int. J. Pharm. Compd. 2020, 24, 501–508. [Google Scholar] [PubMed]
- Brasileiro, A.C.L.; de Oliveira, D.C.; da Silva, P.B.; Rocha, J.K.S.L. Impact of topical nifedipine on wound healing in animal model (pig). J. Vasc. Bras. 2020, 19, e20190092. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mojiri-Forushani, H. The role of calcium channel blockers in wound healing. Iran. J. Basic Med. Sci. 2018, 21, 1198–1199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bagheri, M.; Jahromi, B.M.; Mirkhani, H.; Solhjou, Z.; Noorafshan, A.; Zamani, A.; Amirghofran, Z. Azelnidipine, a new calcium channel blocker, promotes skin wound healing in diabetic rats. J. Surg. Res. 2011, 169, e101–e107. [Google Scholar] [CrossRef] [Scilit]
- Bhasker, H.; Udupa, S.L.; Udupa, A.L. Effect of nifedipine and amlodipine on wound healing in rats. Indian J. Physiol. Pharmacol. 2004, 48, 111–114. [Google Scholar] [PubMed]
- Hemmati, A.A.; Forushani, H.M.; Asgari, H.M. Wound healing potential of topical amlodipine in full thickness wound of rabbit. Jundishapur J. Nat. Pharm. Prod. 2014, 9, e15638. [Google Scholar] [CrossRef] [Scilit]
- Schwentker, A.; Billiar, T.R. Nitric oxide and wound repair. Surg. Clin. N. Am. 2003, 83, 521–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luo, J.D.; Chen, A.F. Nitric oxide: A newly discovered function on wound healing. Acta Pharmacol. Sin. 2005, 26, 259–264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Witte, M.B.; Kiyama, T.; Barbul, A. Nitric oxide enhances experimental wound healing in diabetes. Br. J. Surg. 2002, 89, 1594–1601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shabani, M.; Pulfer, S.K.; Bulgrin, J.P.; Smith, D.J. Enhancement of wound repair with a topically applied nitric oxide-releasing polymer. Wound Repair. Regen. 1996, 4, 353–362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amadeu, T.P.; Seabra, A.B.; de Oliveira, M.G.; Monte-Alto-Costa, A. Nitric oxide donor improves healing if applied on inflammatory and proliferative phase. J. Surg. Res. 2008, 149, 84–93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stallmeyer, B.; Kämpfer, H.; Kolb, N.; Pfeilschifter, J.; Frank, S. The function of nitric oxide in wound repair: Inhibition of inducible nitric oxide-synthase severely impairs wound reepithelialization. J. Investig. Dermatol. 1999, 113, 1090–1098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamasaki, K.; Edington, H.D.J.; McClosky, C.; Tzeng, E.; Lizonova, A.; Kovesdi, I.; Steed, D.L.; Billiar, T.R. Reversal of impaired wound repair in iNOS-deficient mice by topical adenoviral-mediated iNOS gene transfer. J. Clin. Investig. 1998, 101, 967–971. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amadeu, T.P.; Monte-Alto-Costa, A.M. Nitric oxide synthesis inhibition alters rat cutaneous wound healing. J. Cutan. Pathol. 2006, 33, 465–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Norgren, L.; Alwmark, A.; Angqvist, K.A.; Hedberg, B.; Bergqvist, D.; Takolander, R.; Claes, G.; Lundell, A.; Holm, J.; Jivegård, L.; et al. A stable prostacyclin analogue (iloprost) in the treatment of ischaemic ulcers of the lower limb: A Scandinavian-Polish placebo-controlled, randomised multicenter study. Eur. J. Vasc. Surg. 1990, 4, 463–467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pedersen, A.K.; FitzGerald, G.A. Dose-related kinetics of aspirin: Presystemic acetylation of platelet cyclooxygenase. N. Engl. J. Med. 1984, 311, 1206–1211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gunji, H.; Ono, I.; Tateshita, T.; Kaneko, F. Clinical effectiveness of an ointment containing prostaglandin E1 for the treatment of burn wounds. Burns 1996, 22, 399–405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kristensen, K.E.; Gislason, G.H.; Torp-Pedersen, C.; Rasmussen, H.B.; Hansen, P.R. Risk of hemorrhagic events in patients co-treated with clopidogrel and angiotensin-converting enzyme inhibitors after myocardial infarction. Eur. Heart J. 2013, 34, P2513. [Google Scholar] [CrossRef] [Scilit]
- Chen, R.; Suchard, M.A.; Krumholz, H.M.; Schuemie, M.J.; Shea, S.; Duke, J.; Pratt, N.; Reich, C.G.; Madigan, D.; You, S.C.; et al. Comparative first-line effectiveness and safety of ACE (angiotensin-converting enzyme) inhibitors and angiotensin receptor blockers: A multinational cohort study. Hypertension 2021, 78, 591–603. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- The Heart Outcomes Prevention Evaluation Study Investigators. Effects of an angiotensin-converting–enzyme inhibitor, ramipril, on cardiovascular events in high-risk patients. N. Engl. J. Med. 2000, 342, 145–153. [CrossRef] [Scilit] [PubMed]
- Pfeffer, M.A.; McMurray, J.J.; Velazquez, E.J.; Rouleau, J.-L.; Køber, L.; Maggioni, A.P.; Solomon, S.D.; Swedberg, K.; Van de Werf, F.; White, H.; et al. Valsartan, captopril, or both in myocardial infarction complicated by heart failure, left ventricular dysfunction, or both. N. Engl. J. Med. 2003, 349, 1893–1906. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chae, Y.K.; Khemasuwan, D.; Dimou, A.; Neagu, S.; Chebrolu, L.; Gupta, S.; Carpio, A.; Kim, J.; Yun, J.H.; Smyrlis, A.; et al. Inhibition of renin angiotensin axis may be associated with reduced risk of developing venous thromboembolism in patients with atherosclerotic disease. PLoS ONE 2014, 9, e87813. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Hannedouche, T.; Godin, M.; Fries, D.; Fillastre, J.P. Acute renal thrombosis induced by angiotensin-converting enzyme inhibitors in patients with renovascular hypertension. Nephron 1991, 57, 230–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dussol, B.; Nicolino, F.; Brunet, P.; Leonetti, F.; Siles, S.; Berland, Y. Acute transplant artery thrombosis induced by angiotensin-converting inhibitor in a patient with renovascular hypertension. Nephron 1994, 66, 102–104. [Google Scholar] [CrossRef] [Scilit]
- Kerbert, A.J.C.; Chiang, F.W.T.; van der Werf, M.; Stijnen, T.; Slingerland, H.; Verspaget, H.W.; van Hoek, B.; Coenraad, M.J. Hemodynamic response to primary prophylactic therapy with nonselective β-blockers is related to a reduction of first variceal bleeding risk in liver cirrhosis: A meta-analysis. Eur. J. Gastroenterol. Hepatol. 2017, 29, 380–387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, S.; Li, Z.; Yang, T.; Li, L.; Song, X.; Hao, Y.; Smith, S.C.; Fonarow, G.C.; Morgan, L.; Liu, J.; et al. Association between early oral β-blocker therapy and risk for in-hospital major bleeding after percutaneous coronary intervention for acute coronary syndrome: Findings from CCC-ACS project. Eur. Heart J. Qual. Care Clin. Outcomes 2023, 9, 293–302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Asadbeygi, A.; Lee, S.; Kovalchin, J.; Hatoum, H. Effect of beta blockers on the hemodynamics and thrombotic risk of coronary artery aneurysms in Kawasaki disease. J. Cardiovasc. Transl. Res. 2023, 16, 852–861. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Y.; Chan, E.W.; Leung, W.K.; Anand, S.; Wong, I.C.K. Systematic review with meta-analysis: The association between the use of calcium channel blockers and gastrointestinal bleeding. Aliment. Pharmacol. Ther. 2015, 41, 1246–1255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sakakibara, F.; Ueda, S.; Uchida, K.; Kinjo, N.; Arai, H.; Nezu, M.; Morimoto, T. Association between dihydropyridine calcium channel blockers and ischemic strokes in patients with nonvalvular atrial fibrillation. Hypertens. Res. 2022, 45, 1028–1036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uchida, K.; Ueda, S.; Sakakibara, F.; Kinjo, N.; Nezu, M.; Arai, H.; Morimoto, T. Statins reduce bleeding risk in patients taking oral anticoagulants for nonvalvular atrial fibrillation: A retrospective registry study. Am. J. Cardiovasc. Drugs 2023, 23, 89–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Agarwal, V.; Phung, O.J.; Tongbram, V.; Bhardwaj, A.; Coleman, C.I. Statin use and the prevention of venous thromboembolism: A meta-analysis. Int. J. Clin. Pract. 2010, 64, 1375–1383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Radomski, M.W.; Palmer, R.M.J.; Moncada, S. An L-arginine/nitric oxide pathway present in human platelets regulates aggregation. Proc. Natl. Acad. Sci. USA 1990, 87, 5193–5197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Freedman, J.E.; Loscalzo, J. Nitric oxide and its relationship to thrombotic disorders. J. Thromb. Haemost. 2003, 1, 1183–1188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, J.; Ye, J.; Zhu, J.; Xiao, Z.; He, C.; Shi, H.; Wang, Y.; Lin, C.; Zhang, H.; Zhao, Y.; et al. Heparin-based coacervate of FGF2 improves dermal regeneration by asserting a synergistic role with cell proliferation and endogenous facilitated VEGF for cutaneous wound healing. Biomacromolecules 2016, 17, 2168–2177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galvan, L. Effects of heparin on wound healing. J. Wound Ostomy Cont. Nurs. 1996, 23, 224–226. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kohyama, K.; Kato, H.; Okada, H.; Ishihara, T.; Yasue, Y.; Kamidani, R.; Suzuki, K.; Miyake, T.; Okuda, H.; Shibata, H.; et al. Concomitant heparin use promotes skin graft donor site healing by basic fibroblast growth factor: A pilot prospective randomized controlled study. Contemp. Clin. Trials Commun. 2024, 42, 101375. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Matzsch, T.; Bergqvist, D.; Blomquist, P.; Jiborn, H. Influence of standard heparin or low molecular weight heparin on healing of abdominal wounds and colonic anastomoses in rats. Acta Chir. Scand. 1987, 153, 593–598. [Google Scholar] [PubMed]
- Civelek, A.; Ak, K.; Kurtkaya, O.; Tekeli, A.; Isbir, S.; Nargileci, E.; Arsan, S.; Sav, A. Effect of a low molecular weight heparin molecule, dalteparin, on cellular apoptosis and inflammatory process in an incisional wound-healing model. Surg. Today 2007, 37, 406–411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ozdamar Fuad, O.; Yildirim, A.O.; Gulcek, M.; Unal, V.S.; Karakuyu, A.; Ozlu, K.; Ucaner, A. The effect of prophylactic dose of a low molecular weight heparin on skin wound healing of rats. Acta Cir. Bras. 2009, 24, 471–475. [Google Scholar] [CrossRef] [Scilit]
- Seebauer, C.; Hanafieh, F.; Wolff, J.; Metelmann, H.-R.; Vollmer, M. Influence of anticoagulant concomitant medication on wound healing: Analysis of a multicentre cohort of 212 patients with a uniform wound model. Br. J. Clin. Pharmacol. 2025, 91, 2583–2589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lindner, T.; Cockbain, A.J.; El Masry, M.A.; Katonis, P.; Tsiridis, E.; Schizas, C.; Tsiridis, E. The effect of anticoagulant pharmacotherapy on fracture healing. Expert. Opin. Pharmacother. 2008, 9, 1169–1187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ad-El, D.D.; Meirovitz, A.; Weinberg, A.; Kogan, L.; Arieli, D.; Neuman, A.; Linton, D. Warfarin skin necrosis: Local and systemic factors. Br. J. Plast. Surg. 2000, 53, 624–626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, L.; Elliott, S.N.; Cirino, G.; Buret, A.; Ignarro, L.J.; Wallace, J.L. Platelets modulate gastric ulcer healing: Role of endostatin and vascular endothelial growth factor release. Proc. Natl. Acad. Sci. USA 2001, 98, 6470–6475. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- dos Santos, J.S.; Monte-Alto-Costa, A. Female, but not male, mice show delayed cutaneous wound healing following aspirin administration. Clin. Exp. Pharmacol. Physiol. 2013, 40, 90–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takahashi, K.; Nosaka, T.; Murata, Y.; Sugata, R.; Akazawa, Y.; Tanaka, T.; Naito, T.; Matsuda, H.; Ohani, M.; Suto, H.; et al. Influence of antiplatelet drugs on gastric ulcer healing after endoscopic submucosal dissection in patients with early gastric cancer. DEN Open 2025, 5, e70070. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Chan, J.C.Y.; Duszczyszyn, D.A.; Castellino, F.J.; Ploplis, V.A. Accelerated skin wound healing in plasminogen activator inhibitor-1-deficient mice. Am. J. Pathol. 2001, 159, 1681–1688. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Lund, L.R.; Rømer, J.; Bugge, T.H.; Nielsen, B.S.; Frandsen, T.L.; Degen, J.L.; Stephens, R.W.; Danø, K. Functional overlap between two classes of matrix-degrading proteases in wound healing. EMBO J. 1999, 18, 4645–4656. [Google Scholar] [CrossRef] [Scilit]
- Lund, L.R.; Green, K.A.; Stoop, A.A.; Ploug, M.; Almholt, K.; Lilla, J.; Nielsen, B.S.; Christensen, I.J.; Craik, C.S.; Werb, Z.; et al. Plasminogen activation independent of uPA and tPA maintains wound healing in gene-deficient mice. EMBO J. 2006, 25, 2686–2697. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Gailani, D.; Cheng, Q.; Ivanov, I.S. Murine models in the evaluation of heparan sulfate-based anticoagulants. Methods Mol. Biol. 2015, 1229, 483–496. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Palm, M.; Mattsson, C.; Svahn, C.M.; Weber, M. Bleeding times in rats treated with heparin, heparin fragments of high and low anticoagulant activity and chemically modified heparin fragments of low anticoagulant activity. Thromb. Haemost. 1990, 64, 127–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tuthill, D.D.; Bayer, V.; Gallagher, A.M.; Drohan, W.N.; MacPhee, M.J. Assessment of topical hemostats in a renal hemorrhage model in heparinized rats. J. Surg. Res. 2001, 95, 126–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Foerch, C.; Arai, K.; Jin, G.; Park, K.P.; Pallast, S.; van Leyen, K.; Lo, E.H. Experimental model of warfarin-associated intracerebral hemorrhage. Stroke 2008, 39, 3397–3404. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elg, M.; Gustafsson, D.; Carlsson, S. Antithrombotic effects and bleeding time of thrombin inhibitors and warfarin in the rat. Thromb. Res. 1999, 94, 187–197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- López-Belmonte, J.; Whittle, B.J.R.; Moncada, S. The actions of nitric oxide donors in the prevention or induction of injury to the rat gastric mucosa. Br. J. Pharmacol. 1993, 108, 73–78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Whittle, B.J.R.; Boughton-Smith, N.K.; Moncada, S. Biosynthesis and role of the endothelium-derived vasodilator, nitric oxide, in the gastric mucosa. Ann. N. Y. Acad. Sci. 1992, 664, 126–139. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palmer, R.M.; Ferrige, A.G.; Moncada, S. Nitric oxide release accounts for the biological activity of endothelium-derived relaxing factor. Nature 1987, 327, 524–526. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sikiric, P.; Barisic, I.; Udovicic, M.; Lovrić Benčić, M.; Balenovic, D.; Strinic, D.; Zivanovic Posilovic, G.; Uzun, S.; Vranes, H.; Krezic, I.; et al. Conventional antiarrhythmics class I–IV, late INa inhibitors, IKs enhancers, RyR2 stabilizers, gap junction modulators, atrial-selective antiarrhythmics, and stable gastric pentadecapeptide BPC 157 as useful cytoprotective therapy in arrhythmias. Pharmaceuticals 2026, 19, 235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blackshear, J.L.; Odell, J.A. Appendage obliteration to reduce stroke in cardiac surgical patients with atrial fibrillation. Ann. Thorac. Surg. 1996, 61, 755–759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lip, G.Y.H.; Proietti, M.; Potpara, T.; Mansour, M.; Savelieva, I.; Tse, H.F.; Goette, A.; Camm, A.J.; Blomstrom-Lundqvist, C.; Gupta, D.; et al. Atrial fibrillation and stroke prevention: 25 years of research at EP Europace journal. Europace 2023, 25, euad226. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guazzi, M.; Arena, R. Endothelial dysfunction and pathophysiological correlates in atrial fibrillation. Heart 2009, 95, 102–106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corban, M.T.; Toya, T.; Ahmad, A.; Lerman, L.O.; Lee, H.-C.; Lerman, A. Atrial fibrillation and endothelial dysfunction: A potential link? Mayo Clin. Proc. 2021, 96, 1609–1621. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badimon, L.; Cubedo, J. Hypercoagulability and atrial fibrillation: A two-way road? Eur. Heart J. 2017, 38, 51–52. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balenovic, D.; Bencic, M.L.; Udovicic, M.; Simonji, K.; Hanzevacki, J.S.; Barisic, I.; Kranjcevic, S.; Prkacin, I.; Coric, V.; Brcic, L.; et al. Inhibition of methyldigoxin-induced arrhythmias by pentadecapeptide BPC 157: A relation with NO-system. Regul. Pept. 2009, 156, 83–89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barisic, I.; Balenovic, D.; Klicek, R.; Radic, B.; Nikitovic, B.; Drmic, D.; Udovicic, M.; Strinic, D.; Bardak, D.; Berkopic, L.; et al. Mortal hyperkalemia disturbances in rats are NO-system related: The life saving effect of pentadecapeptide BPC 157. Regul. Pept. 2013, 181, 50–66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balenovic, D.; Barisic, I.; Prkacin, I.; Horvat, I.; Udovicic, M.; Uzun, S.; Strinic, D.; Pevec, D.; Drmic, D.; Radic, B.; et al. Mortal furosemide-hypokalemia-disturbances in rats NO-system related shorten survival by L-NAME. Therapy benefit with BPC 157 peptide more than with L-arginine. J. Clin. Exp. Cardiolog. 2012, 3, 7. [Google Scholar] [CrossRef]
- Lozic, M.; Stambolija, V.; Krezic, I.; Dugandzic, A.; Zivanovic-Posilovic, G.; Gojkovic, S.; Kovacevic, J.; Vrdoljak, L.; Mirkovic, I.; Kokot, A.; et al. In relation to NO-system, stable pentadecapeptide BPC 157 counteracts lidocaine-induced adverse effects in rats and depolarisation in vitro. Emerg. Med. Int. 2020, 2020, 6805354. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Zivanovic-Posilovic, G.; Balenovic, D.; Barisic, I.; Strinic, D.; Stambolija, V.; Udovicic, M.; Uzun, S.; Drmic, D.; Vlainic, J.; Bencic, M.L.; et al. Stable gastric pentadecapeptide BPC 157 and bupivacaine. Eur. J. Pharmacol. 2016, 793, 56–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stambolija, V.; Perleta Stambolija, T.; Katancic Holjevac, J.; Murselovic, T.; Radonic, J.; Duzel, V.; Duplancic, B.; Uzun, S.; Zivanovic-Posilovic, G.; Kolenc, D.; et al. BPC 157: The counteraction of succinylcholine, hyperkalemia, and arrhythmias. Eur. J. Pharmacol. 2016, 781, 83–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strinić, D.; Belosić Halle, Ž.; Luetić, K.; Nedić, A.; Petrović, I.; Sucić, M.; Živanović Posilović, G.; Balenović, D.; Strbe, S.; Udovičić, M.; et al. BPC 157 counteracts QTc prolongation induced by haloperidol, fluphenazine, clozapine, olanzapine, quetiapine, sulpiride, and metoclopramide in rats. Life Sci. 2017, 186, 66–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Udovicic, M.; Sever, M.; Kavur, L.; Loncaric, K.; Barisic, I.; Balenovic, D.; Zivanovic Posilovic, G.; Strinic, D.; Uzun, S.; Batelja Vuletic, L.; et al. Stable gastric pentadecapeptide BPC 157 therapy for monocrotaline-induced pulmonary hypertension in rats leads to prevention and reversal. Biomedicines 2021, 9, 822. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Medvidovic-Grubisic, M.; Stambolija, V.; Kolenc, D.; Katancic, J.; Murselovic, T.; Plestina-Borjan, I.; Strbe, S.; Drmic, D.; Barisic, I.; Sindic, A.; et al. Hypermagnesemia disturbances in rats, NO-related: Pentadecapeptide BPC 157 abrogates, L-NAME and L-arginine worsen. Inflammopharmacology 2017, 25, 439–449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bjerkelund, C.J.; Orning, O.M. The efficacy of anticoagulant therapy in preventing embolism related to D.C. electrical conversion of atrial fibrillation. Am. J. Cardiol. 1969, 23, 208–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lip, G.Y.H.; Nieuwlaat, R.; Pisters, R.; Lane, D.A.; Crijns, H.J.G.M. Refining clinical risk stratification for predicting stroke and thromboembolism in atrial fibrillation using a novel risk factor-based approach: The Euro Heart Survey on Atrial Fibrillation. Chest 2010, 137, 263–272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weigner, M.J.; Caulfield, T.A.; Danias, P.G.; Silverman, D.I.; Manning, W.J. Risk for clinical thromboembolism associated with conversion to sinus rhythm in patients with atrial fibrillation lasting less than 48 hours. Ann. Intern. Med. 1997, 126, 615–620. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gallagher, M.M.; Hennessy, B.J.; Edvardsson, N.; Hart, C.M.; Shannon, M.S.; Obel, O.A.; Al-Saady, N.M.; Camm, A.J. Embolic complications of direct current cardioversion of atrial arrhythmias: Association with low intensity of anticoagulation at the time of cardioversion. J. Am. Coll. Cardiol. 2002, 40, 926–933. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ariëns, E.J. Intrinsic activity: Partial agonists and partial antagonists. J. Cardiovasc. Pharmacol. 1983, 5, S8–S15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cruickshank, J.M. Are we misunderstanding β-blockers? Int. J. Cardiol. 2007, 120, 10–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taddei, S.; Tsabedze, N.; Tan, R.-S. β-blockers are not all the same: Pharmacologic similarities and differences, potential combinations and clinical implications. Curr. Med. Res. Opin. 2024, 40, 15–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jones, K.E.; Hayden, S.L.; Meyer, H.R.; Sandoz, J.L.; Arata, W.H.; Dufrene, K.; Ballaera, C.; Lopez Torres, Y.; Griffin, P.; Kaye, A.M.; et al. The evolving role of calcium channel blockers in hypertension management: Pharmacological and clinical considerations. Curr. Issues Mol. Biol. 2024, 46, 6315–6327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- January, C.T.; Wann, L.S.; Calkins, H.; Chen, L.Y.; Cigarroa, J.E.; Cleveland, J.C., Jr.; Ellinor, P.T.; Ezekowitz, M.D.; Field, M.E.; Furie, K.L.; et al. 2019 AHA/ACC/HRS focused update of the 2014 AHA/ACC/HRS guideline for the management of patients with atrial fibrillation: A report of the American College of Cardiology/American Heart Association task force on clinical practice guidelines and the Heart Rhythm Society in collaboration with the Society of Thoracic Surgeons. Circulation 2019, 140, e125–e151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dibner-Dunlap, M.E.; Smith, M.L.; Kinugawa, T.; Thames, M.D. Enalaprilat augments arterial and cardiopulmonary baroreflex control of sympathetic nerve activity in patients with heart failure. J. Am. Coll. Cardiol. 1996, 27, 317–324. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kida, T.; Sawada, K.; Kobayashi, K.; Hori, M.; Ozaki, H.; Murata, T. Diverse effects of prostaglandin E2 on vascular contractility. Heart Vessel. 2014, 29, 390–395. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hristovska, A.-M.; Rasmussen, L.E.; Hansen, P.B.L.; Nielsen, S.S.; Nüsing, R.M.; Narumiya, S.; Vanhoutte, P.; Skøtt, O.; Jensen, B.L. Prostaglandin E2 induces vascular relaxation by E-prostanoid 4 receptor-mediated activation of endothelial nitric oxide synthase. Hypertension 2007, 50, 525–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Herring, N.; Paterson, D.J. Nitric oxide–cGMP pathway facilitates acetylcholine release and bradycardia during vagal nerve stimulation in the guinea-pig in vitro. J. Physiol. 2001, 535, 507–518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choate, J.K.; Danson, E.J.; Morris, J.F.; Paterson, D.J. Peripheral vagal control of heart rate is impaired in neuronal NOS knockout mice. Am. J. Physiol. Heart Circ. Physiol. 2001, 281, H2310–H2317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pechanova, O.; Vrankova, S.; Cebova, M. Chronic L-NAME treatment produces hypertension by different mechanisms in peripheral tissues and brain: Role of central eNOS. Physiol. Res. 2009, 58, 291–299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wibawa, K.; Dewangga, R.; Nastiti, K.S.; Syah, P.A.; Suhendiwijaya, S.; Ariffudin, Y. Prior statin use and the incidence of in-hospital arrhythmia in acute coronary syndrome: A systematic review and meta-analysis. Indian Heart J. 2023, 75, 9–16. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Wanahita, N.; Chen, J.; Bangalore, S.; Shah, K.; Rachko, M.; Coleman, C.I.; Schweitzer, P. The effect of statin therapy on ventricular tachyarrhythmias: A meta-analysis. Am. J. Ther. 2012, 19, 16–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fiedler, L.; Hallsson, L.; Tscharre, M.; Oebel, S.; Pfeffer, M.; Schönbauer, R.; Tokarska, L.; Stix, L.; Haiden, A.; Kraus, J.; et al. Upstream statin therapy and long-term recurrence of atrial fibrillation after cardioversion: A propensity-matched analysis. J. Clin. Med. 2021, 10, 807. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Millar, P.J.; Floras, J.S. Statins and the autonomic nervous system. Clin. Sci. 2014, 126, 401–415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pedersen, T.R. Pleiotropic effects of statins: Evidence against benefits beyond LDL-cholesterol lowering. Am. J. Cardiovasc. Drugs 2010, 10, 10–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Welzig, C.M.; Shin, D.-G.; Park, H.-J.; Kim, Y.-J.; Saul, J.P.; Galper, J.B. Lipid lowering by pravastatin increases parasympathetic modulation of heart rate: Galpha(i2), a possible molecular marker for parasympathetic responsiveness. Circulation 2003, 108, 2743–2746. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gamulin, O.; Oroz, K.; Coric, L.; Krajacic, M.; Skrabic, M.; Dretar, V.; Strbe, S.; Talapko, J.; Juzbasic, M.; Krezic, I.; et al. Fourier transform infrared spectroscopy reveals molecular changes in blood vessels of rats treated with pentadecapeptide BPC 157. Biomedicines 2022, 10, 3130. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Smoday, I.M.; Vukovic, V.; Oroz, K.; Vranes, H.; Kalogjera, L.; Gamulin, O.; Vlainic, J.; Milavic, M.; Sikiric, S.; Nikolac Gabaj, N.; et al. Fourier transform infrared spectroscopic characterization of aortic wall remodeling by stable gastric pentadecapeptide BPC 157 after unilateral adrenalectomy in rats. Pharmaceuticals 2026, 19, 191. [Google Scholar] [CrossRef] [Scilit]
- Mustafa, A.K.; Gadalla, M.M.; Snyder, S.H. Signaling by gasotransmitters. Sci. Signal. 2009, 2, re2. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Seiwerth, S.; Rucman, R.; Turkovic, B.; Sever, M.; Klicek, R.; Radic, B.; Drmic, D.; Stupnisek, M.; Misic, M.; Vuletic, L.B.; et al. BPC 157 and standard angiogenic growth factors: Gastrointestinal tract healing, lessons from tendon, ligament, muscle and bone healing. Curr. Pharm. Des. 2018, 24, 1972–1989. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lie, S.L.; Rognes, I.N. Human and animal models for studying hemorrhagic shock. Scand. J. Trauma. Resusc. Emerg. Med. 2025, 33, 124. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ayyoub, S.; Orriols, R.; Oliver, E.; Tura Ceide, O. Thrombosis models: An overview of common in vivo and in vitro models of thrombosis. Int. J. Mol. Sci. 2023, 24, 2569. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Badimon, L. Models to study thrombotic disorders. Thromb. Haemost. 1997, 78, 667–671. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badimon, L. Atherosclerosis and thrombosis: Lessons from animal models. Thromb. Haemost. 2001, 86, 356–365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Demirtaş, H.; Özer, A.; Yıldırım, A.K.; Dursun, A.D.; Sezen, Ş.C.; Arslan, M. Protective effects of BPC 157 on liver, kidney, and lung distant organ damage in rats with experimental lower-extremity ischemia–reperfusion injury. Medicina 2025, 61, 291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kalogjera, L.; Ries, M.; Baudoin, T.; Ferencic, Z.; Trotic, R.; Pegan, B. Dose-dependent protective effect of BPC 157 on capsaicin-induced rhinitis in rats. Eur. Arch. Otorhinolaryngol. 1997, 254, S9–S11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Veljaca, M.; Lesch, C.A.; Pllana, R.; Sanchez, B.; Chan, K.; Guglietta, A. BPC-15 reduces trinitrobenzene sulfonic acid-induced colonic damage in rats. J. Pharmacol. Exp. Ther. 1995, 272, 417–422. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bódis, B.; Karádi, O.; Németh, P.; Dohoczky, C.; Kolega, M.; Mózsik, G. Evidence for direct cellular protective effect of PL-10 substances (synthesized parts of body protection compound, BPC) and their specificity to gastric mucosal cells. Life Sci. 1997, 61, PL243–PL248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sandor, Z.S.; Vincze, A.; Jadus, M.R.; Dohoczky, C.; Erceg, D.; Brajsa, K.; Kolega, M.; Szabo, S. The protective effect of newly isolated peptide PL-10 in the iodoacetamide colitis model in rats. Gastroenterology 1997, 112, A400. [Google Scholar]
- Sandor, Z.; Vincze, A.; Szabo, S. The protective effect of a recently isolated gastric peptide in acute and chronic gastric injury. FASEB J. 1996, 10, 986. [Google Scholar]
- Jung, Y.H.; Kim, H.; Kim, H.; Kim, E.; Baik, J.; Kang, H. The anti-nociceptive effect of BPC 157 on the incisional pain model in rats. J. Dent. Anesth. Pain. Med. 2022, 22, 97–105. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, S.Y.; Choi, S.R.; Kim, J.H.; Lee, S.C.; Jeong, J.H.; Lee, T.Y. Antinociceptive effect of BPC 157 in the formalin induced pain model. Kosin Med. J. 2021, 36, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Miyake, T.; Kung, C.K.H.; Goldwasser, E. Purification of human erythropoietin. J. Biol. Chem. 1977, 252, 5558–5564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldwasser, E. Erythropoietin and the differentiation of red blood cells. Fed. Proc. 1975, 34, 2285–2292. [Google Scholar] [PubMed]
- Holst, J.J. The physiology of glucagon-like peptide 1. Physiol. Rev. 2007, 87, 1409–1439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Drucker, D.J. The biology of incretin hormones. Cell Metab. 2006, 3, 153–165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nauck, M.A.; Bartels, E.; Ørskov, C.; Ebert, R.; Creutzfeldt, W. Additive insulinotropic effects of GIP and GLP-1 in humans. J. Clin. Endocrinol. Metab. 1993, 76, 912–917. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miyata, A.; Arimura, A.; Dahl, R.R.; Minamino, N.; Uehara, A.; Jiang, L.; Culler, M.D.; Coy, D.H. Isolation of a novel 38 residue-hypothalamic polypeptide which stimulates adenylate cyclase in pituitary cells. Biochem. Biophys. Res. Commun. 1989, 164, 567–574. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Said, S.I. Vasoactive intestinal polypeptide: Biologic role in health and disease. Trends Endocrinol. Metab. 1991, 2, 107–112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harmar, A.J.; Fahrenkrug, J.; Gozes, I.; Laburthe, M.; May, V.; Pisegna, J.R.; Vaudry, D.; Vaudry, H.; Waschek, J.A.; Said, S.I. Pharmacology and functions of receptors for vasoactive intestinal peptide and pituitary adenylate cyclase-activating polypeptide: IUPHAR Review 1. Br. J. Pharmacol. 2012, 166, 4–17. [Google Scholar] [CrossRef] [PubMed]
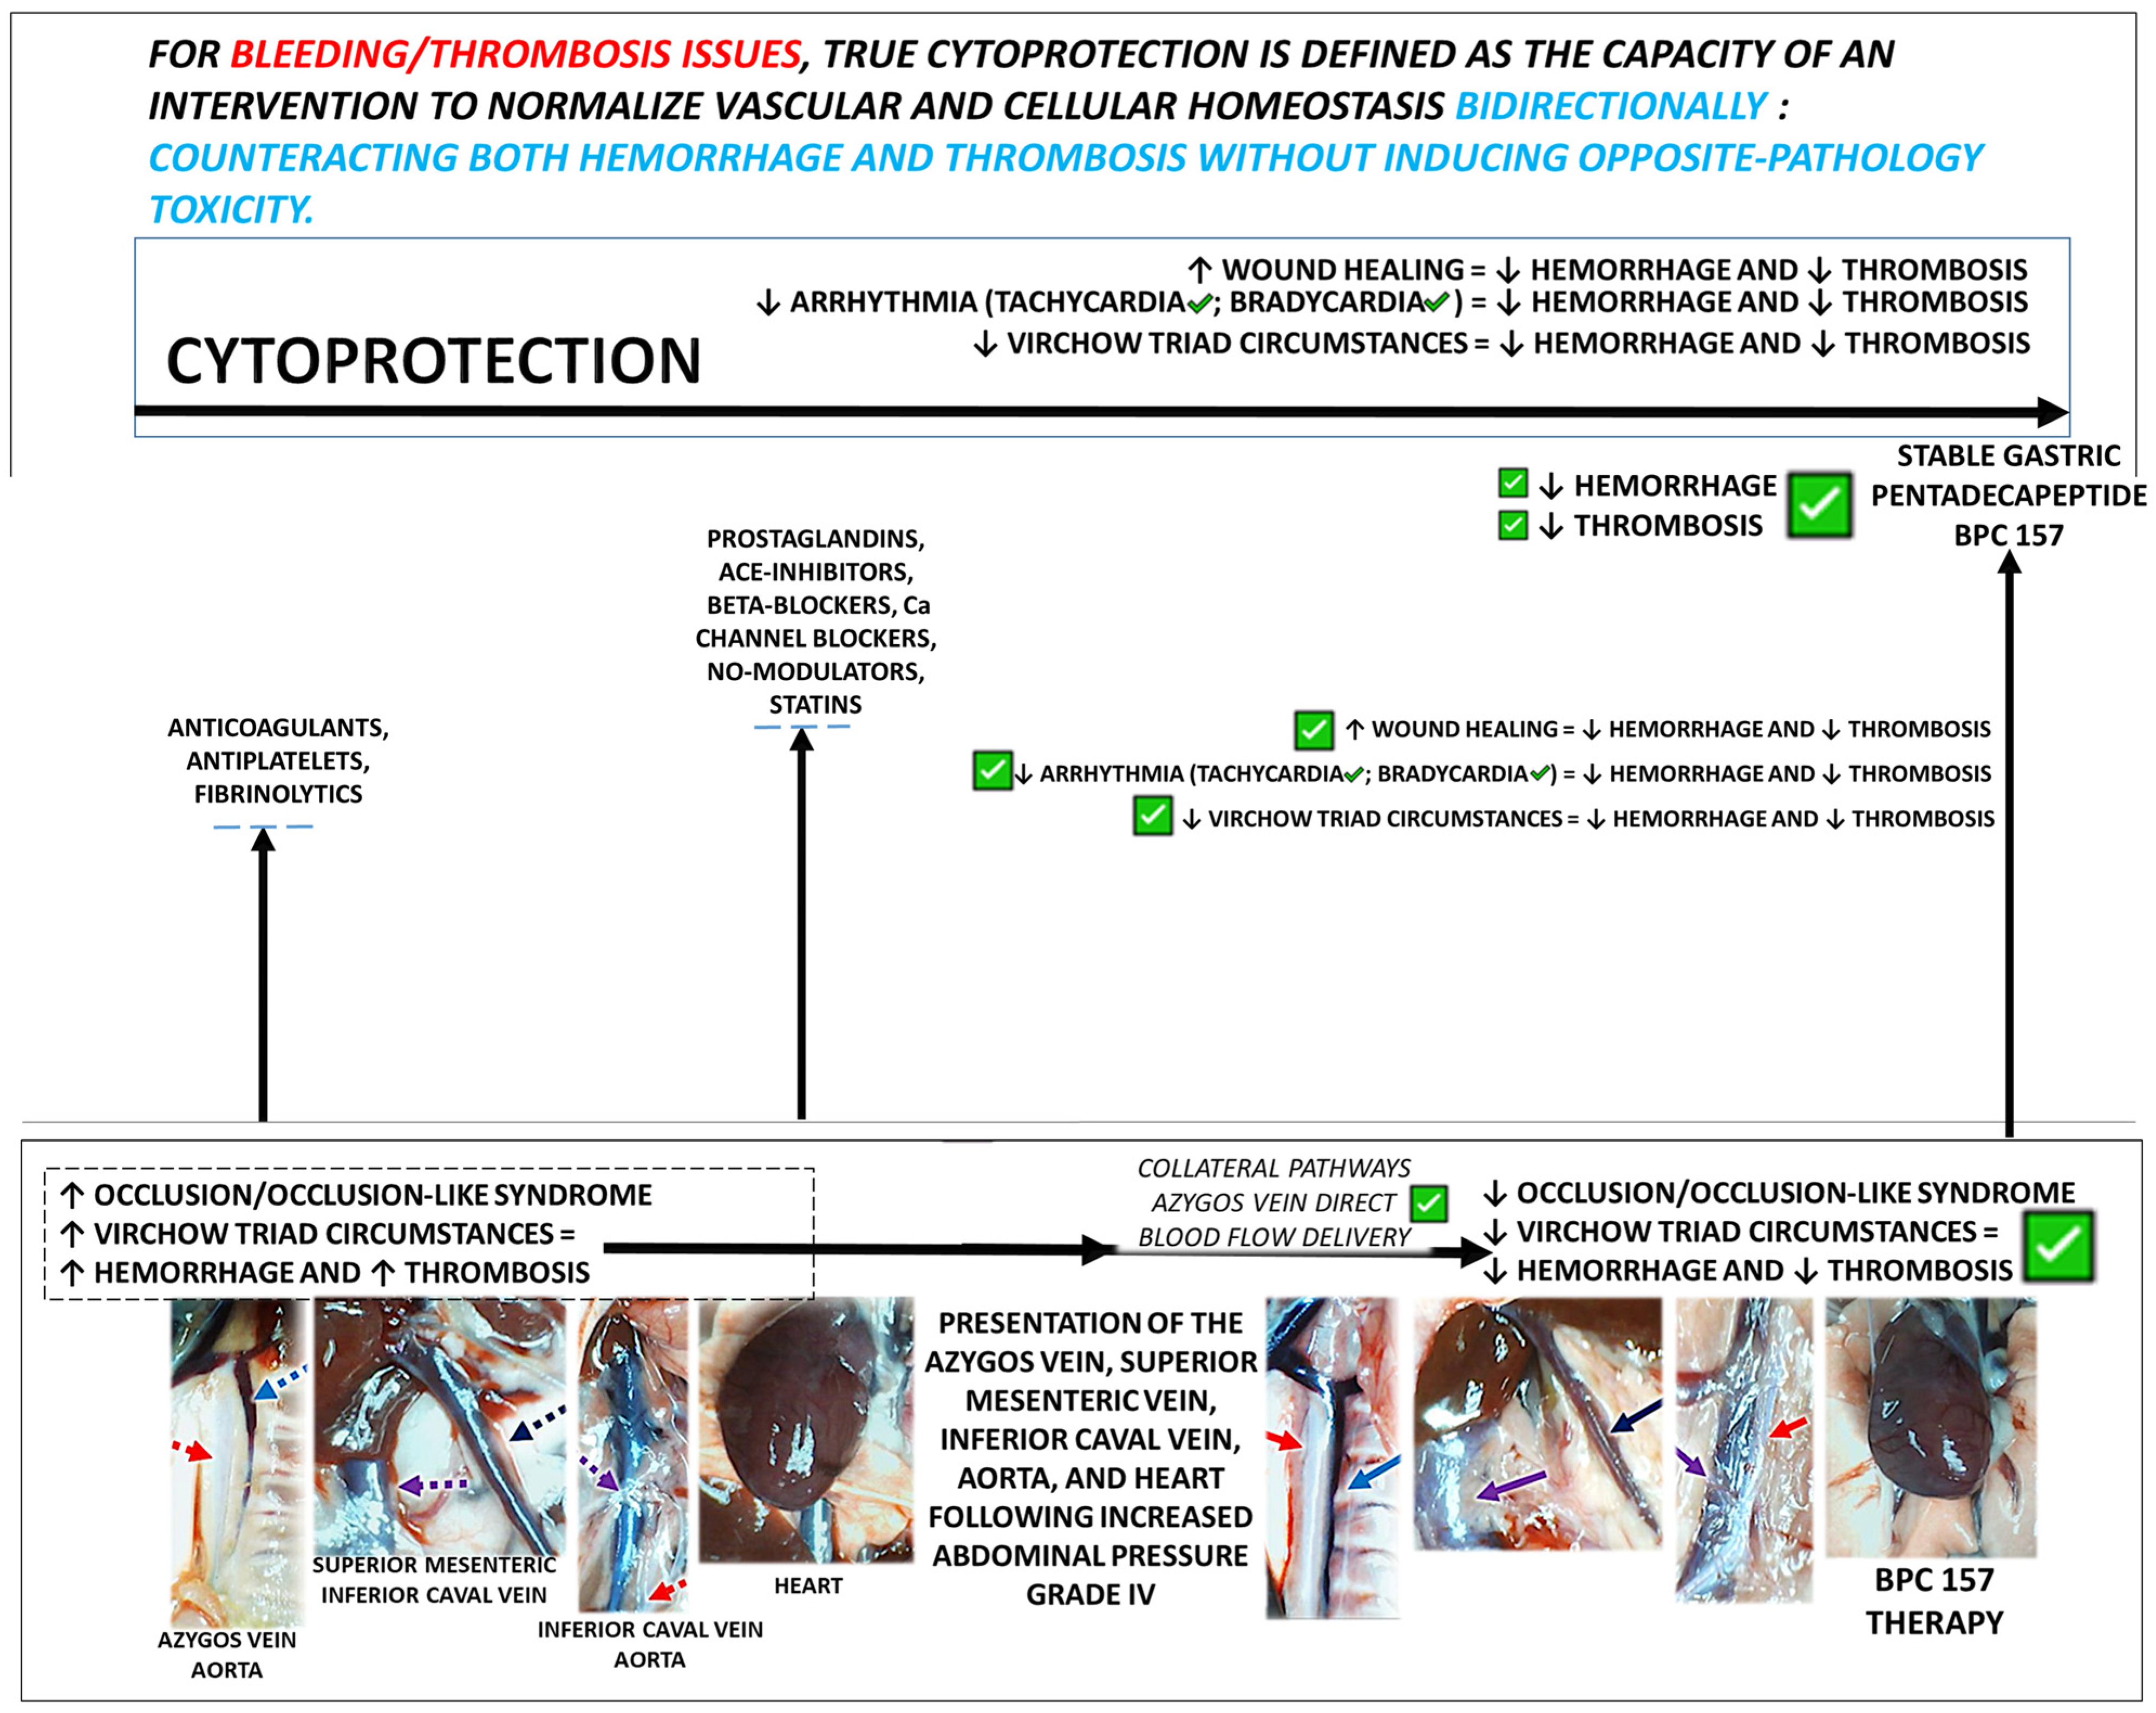

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.