


Abstract
Gingival inflammation represents one of the most prevalent oral inflammatory conditions worldwide and remains a major contributor to oral morbidity. While its classical etiologies are well established, less attention has been paid to inflammatory responses that arise secondary to pulpal injury and tissue damage. Experimental models that allow controlled evaluation of these responses may provide relevant insight into pulp-associated gingival inflammatory processes. Current pharmacological approaches for inflammatory conditions in dentistry, including non-steroidal anti-inflammatory drugs (NSAIDs) and glucocorticoids, are widely used and generally effective. However, their use may be associated with adverse effects in specific clinical contexts, particularly under prolonged or high-dose regimens, highlighting the importance of continued investigation of additional pharmacological strategies. Within this context, pharmacological modulation of inflammatory pathways represents a relevant strategy for exploring alternative therapeutic approaches in pulp-associated gingival inflammation. Accordingly, there is a need to investigate novel molecules with therapeutic potential, such as resiniferatoxin, which has demonstrated anti-inflammatory properties in both in vitro and in vivo experimental models. This study aims to evaluate the anti-inflammatory effect of resiniferatoxin during inflammation of gingival tissue after mechanical pulp damage in a murine experimental model. Six groups of six BALB/c mice were formed as follows: five control groups: a healthy group (HCG), a healthy group treated with resiniferatoxin (RTXHG), a group with pulp damage at 14 h (PGI), two groups with pulp damage treated with ibuprofen (PGIIBU), dexamethasone (PGIDEX) at 14 h, and an experimental group with pulp damage treated with resiniferatoxin (PGIRTX) at 14 h. Gingival inflammation was evaluated after pulp damage was induced through mechanical pulp exposure of the upper first molar. The histopathological parameters of the gingival tissue of all groups were evaluated by hematoxylin and eosin (H&E) staining, while the plasma levels of PGE2 and TNF-α were quantified by ELISA assay. A significant increase in plasma PGE2 and TNF-α levels was observed at 14 h after pulp damage. Subsequently, when treatment with resiniferatoxin was administered, it was observed that this significantly decreased (* p < 0.05) the plasmatic levels of PGE2 and TNF-α, as well as the number of inflammatory cells infiltrated in the gingival tissue 14 h after the pulp damage, similar to treatments with ibuprofen and dexamethasone. Resiniferatoxin exerts an anti-inflammatory effect after pulp damage, significantly decreasing plasma levels of PGE2 and TNF-α, as well as the number of inflammatory cells infiltrated in the gingival tissue, which places resiniferatoxin as a potential drug, in this case, for the treatment of gingival inflammation.
1. Introduction
Pulp exposure and injury is a common phenomenon, caused by various stimuli, such as thermal, chemical, mechanical and microbiological [1], which are capable of inducing an inflammatory response in the pulp tissue [2]. Pulp inflammation is a protective physiological response that seeks to eliminate these harmful stimuli, thus initiating the healing/regeneration process of pulp tissue [3]. This process is mainly characterized by vasodilation and the recruitment and accumulation of inflammatory cells in the pulp tissue [4]. In addition, it also involves the production and release of several inflammatory mediators that influence the regeneration and repair of the dentin-pulp complex [5]. This pulp damage can potentially communicate with the periodontium, producing periodontal lesions and leading to the destruction of a large part of the alveolar bone [6,7].
Endo-periodontal lesions are clinical situations in which the periodontium and root canal of the same tooth become infected, leading to the destruction of the dental attachment apparatus [8], and can be interdependent due to the vascular and anatomical connections between the pulp and the periodontium [9]. Several etiological factors, such as bacteria, as well as contributing factors, such as trauma, root resorption, perforations, cracks and dental malformations, play an important role in the development and progression of endo-periodontal lesions [10]. Endo-periodontal lesions are caused by polymicrobial infections that can originate in the periodontium, pulp tissues, or both, activating an inflammatory response, which is mainly characterized by the activation of a wide variety of cells and the production of pro-inflammatory mediators, such as TNF-α and PGE2, which are involved with the severe development of these pathologies, through the destruction of tissues and the local resorption of the alveolar bone that supports the tooth [11,12,13]. The treatment of endo-periodontal lesions is complex and involves strict control of infection in both periodontal and pulp tissues [14]. This treatment varies depending on the etiology, pathogenesis and correct diagnosis of each specific pathology [10], which consists of root canal treatment when the origin is endodontic and non-surgical and/or a surgical periodontal therapy when the origin is periodontal [15,16,17]. On the other hand, during endo-periodontal lesions, pharmacological therapy for infection control consists of the use of antimicrobials [18,19,20] and antibiotics [21,22], while the pharmacological treatment of inflammation includes non-steroidal anti-inflammatory drugs (NSAIDs) [23,24] and, in some cases, glucocorticoids [25,26]. However, frequent or long-term use of these anti-inflammatory drugs is therapeutically limited due to their side effects [27,28,29]. In this context, there is still a need to develop new alternative therapies that contribute to the treatment of inflammatory diseases. Therefore, there is a wide variety of anti-inflammatory agents available and in development [30], which include biological agents, such as resiniferatoxin, which has demonstrated therapeutic potential for the treatment of inflammation.
Resiniferatoxin is a vanilloid derivative from the cactus-like plant Euphorbia resinifera [31], which is an ultra-potent agonist of the transient receptor potential vanilloid (TRPV)-1, with a unique spectrum of pharmacological action, since its therapeutic window is wide, allowing complete desensitization and inactivation of TRPV-1, decreasing the perception of pain and neurogenic inflammation [32]. In this context, diverse studies have reported that resiniferatoxin exhibits anti-inflammatory properties in both in vitro and in vivo models [29,33]. In the field of dentistry, a recent study evaluated the anti-inflammatory effect of resiniferatoxin in an experimental model of pulp inflammation in mice, in which it was observed that resiniferatoxin was capable of significantly decreasing plasma levels of pro-inflammatory mediators, as well as the number of inflammatory cells infiltrated in the pulp tissue [34]. Based on this rationale, we hypothesized that systemic administration of resiniferatoxin would attenuate gingival inflammatory cell infiltration and reduce plasma levels of PGE2 and TNF-α following mechanical pulp injury in a murine experimental model. Given these findings, and the need to search for new therapeutic alternatives for the treatment of inflammatory diseases in the field of dentistry, the aim of this study was to evaluate the anti-inflammatory effect of resiniferatoxin during inflammation of gingival tissue after mechanical pulp damage in a murine experimental model.
2. Results
2.1. Plasma Levels of PGE2, TNF-α, and Histopathology in Gingival Tissue: 14 Hours After Pulp Damage
Plasma levels of PGE2 and TNF-α were quantitatively determined by ELISA immunoassay, and histopathology of gingival tissue was evaluated 14 h after pulp damage in the control groups. It was observed that at 14 h (PGI group) after pulp damage, plasma levels of PGE2 (113 ± 5 pg/mL) increased significantly (* p < 0.05) compared to the HCG group (62 ± 5 pg/mL), while when compared to the RTXHG group, a significant increase (* p < 0.05) in plasma levels of PGE2 (63 ± 4.0 pg/mL) was observed (Figure 1d). Regarding TNF-α, it was observed that at 14 h (PGI group) after pulp damage, plasma levels (156 ± 7 pg/mL) increased significantly (* p < 0.05) compared to the HCG (91 ± 7 pg/mL) and RTXHG (88 ± 5.0 pg/mL) groups (Figure 1e). Furthermore, no statistically significant differences were found in plasma levels of TNF-α and PGE2 between the HCG and RTXHG groups.
Figure 1.
Induction of pulp damage (a) and illustration of the methodological summary (b). Histopathology of gingival tissue at 14 h after pulp damage (c). Representative histological images are shown; quantitative analysis focused on inflammatory cell infiltration within the connective tissue. Plasma levels of PGE2 (d) and TNF–α (e) at 14 h after pulp damage. Number of infiltrating inflammatory cells in gingival tissue at 14 h after pulp damage (f). Black arrows indicate infiltrating inflammatory cells. Values are represented as mean ± SD per group, indicating the level of significance (* p < 0.05). ns: not significant. HCG: healthy groups. RTXHG: healthy groups treated with resiniferatoxin. PGI: groups with pulp damage at 14 h.
Histologically, in both HCG and RTXHG groups, a basal level of infiltrated inflammatory cells (3 ± 1.0 IIC/TAU and 1 ± 0.6 IIC/TAU, respectively) was observed, without the presence of edema. Histological sections showed perigingivial soft tissues (skeletal muscle, mature adipose tissue, gingival mucosa and adnexa) without alterations, while in the PGI group it was observed that, at the level of the subepithelial lamina propria, there was the presence of chronic inflammatory infiltrate (5 ± 2.0 IIC/TAU, * p < 0.05), with mild and focal lympho-plasmacytic predominance (Figure 1c,f). No histological features of coagulative necrosis or extensive tissue destruction were identified in the gingival specimens.
2.2. Effect of the Treatment with Ibuprofen, Dexamethasone and Resiniferatoxin on the Plasma Levels of PGE2, TNF-α, and Histopathology in Gingival Tissue: 14 Hours After Pulp Damage
At 14 h after pulp damage, PGE2 levels were observed to decrease significantly (* p < 0.05) in the groups treated with ibuprofen (PGIIBU, 69 ± 9 pg/mL), dexamethasone (PGIDEX, 71 ± 11 pg/mL) and resiniferatoxin (PGIRTX, 72 ± 10 pg/mL), compared to the PGI group. Compared with the HCG group, all three treatments showed similar plasma levels of PGE2 (Figure 2a–c). Similarly, it was observed that at 14 h after pulp damage, treatments with ibuprofen (PGIIBU, 79 ± 4 pg/mL), dexamethasone (PGIDEX, 75 ± 6 pg/mL) and resiniferatoxin (PGIRTX, 75 ± 3 pg/mL) significantly decreased (* p < 0.05) plasma levels of TNF-α, compared to the PGI group. Compared with the HCG group, ibuprofen and dexamethasone treatments showed similar plasma levels of TNF-α, except in the group treated with resiniferatoxin, which showed plasma levels of TNF-α lower (* p < 0.05) than the plasma levels of TNF-α of the HCG group (Figure 2d–f).
Figure 2.
Plasma levels of PGE2 at 14 h after pulp damage of the groups treated with (a) ibuprofen, (b) dexamethasone and (c) resiniferatoxin. Plasma levels of TNF–α at 14 h after pulp damage of the groups treated with (d) ibuprofen, (e) dexamethasone and (f) resiniferatoxin. Values are represented as mean ± SD per group, indicating the level of significance (* p < 0.05). ns: not significant. HCG: healthy groups. PGI: groups with pulp damage at 14 h. PGIIBU: groups with pulp damage treated with ibuprofen at 14 h. PGIDEX: groups with pulp damage treated with dexamethasone at 14 h. PGIRTX: experimental groups with pulp damage treated with resiniferatoxin at 14 h.
Histologically, it was observed that in treatments with ibuprofen (PGIIBU, 3 ± 1 IIC/TAU), dexamethasone (PGIDEX, 4 ± 1 IIC/TAU) and resiniferatoxin (PGIRTX, 4 ± 1 IIC/TAU), the infiltrate of inflammatory cells decreased significantly (* p < 0.05) compared to PGI group, presenting a mild focal inflammatory process. (Figure 3a–c). Furthermore, it was observed that in the PGIIBU and PGIDEX groups the inflammatory infiltrate was restricted to the subepithelial level, while in the PGIRTX group the inflammatory infiltrate was located at the level of the musculoskeletal tissue (Figure 3d), without histological evidence of coagulative necrosis.
Figure 3.
Number of infiltrated inflammatory cells during gingival tissue inflammation at 14 h after pulp damage in the groups treated with (a) ibuprofen, (b) dexamethasone, and (c) resiniferatoxin. (d) Representative histopathological images during gingival tissue inflammation at 14 h after pulp damage, in the groups treated with ibuprofen, dexamethasone, and resiniferatoxin. Variation in tissue orientation may result in differential visualization of epithelial and connective tissue layers across fields. Quantitative analysis was performed on standardized fields irrespective of epithelial representation, focusing exclusively on inflammatory cell infiltration within the connective tissue. Black arrows indicate infiltrating inflammatory cells. Values are represented as mean ± SD per group, indicating the level of significance (* p < 0.05). ns: not significant. HCG: healthy groups. RTXHG: healthy groups treated with resiniferatoxin. PGI: groups with pulp damage at 14 h. PGIIBU: groups with pulp damage treated with ibuprofen at 14 h. PGIDEX: groups with pulp damage treated with dexamethasone at 14 h. PGIRTX: experimental groups with pulp damage treated with resiniferatoxin at 14 h.
Finally, the anti-inflammatory effect of the three treatments, ibuprofen (PGIIBU), dexamethasone (PGIDEX), and resiniferatoxin (PGIRTX), was compared. Regarding the level of proinflammatory cytokines in plasma, it was observed that there were no statistically significant differences in the plasma levels of PGE2 and TNF-α between the groups treated with ibuprofen (PGIIBU), dexamethasone (PGIDEX), and resiniferatoxin (PGIRTX), showing a similar anti-inflammatory effect, 14 h after pulp damage (Figure 4a–c). At the histological level, 14 h after pulp damage, a greater anti-inflammatory effect of treatments with ibuprofen (PGIIBU) and dexamethasone (PGIDEX) was observed, since both treatments significantly reduced the inflammatory infiltrate in the gingival tissue, compared to treatment with resiniferatoxin (PGIRTX). However, no significant difference in inflammatory infiltrate was observed between ibuprofen (PGIIBU) and dexamethasone (PGIDEX) treatments (Figure 4d).
Figure 4.
Comparison of the anti-inflammatory effect of treatments with ibuprofen (a), dexamethasone (b) and resiniferatoxin (c) on plasma levels of PGE2 and TNF-α at 14 h after pulp damage. (d) Representative histopathological images during gingival tissue inflammation at 14 h after pulp damage, in the groups treated with ibuprofen, dexamethasone, and resiniferatoxin. Variation in tissue orientation may result in differential visualization of epithelial and connective tissue layers across fields. Quantitative analysis was performed on standardized fields irrespective of epithelial representation, focusing exclusively on inflammatory cell infiltration within the connective tissue. Black arrows indicate infiltrating inflammatory cells. Values are represented as mean ± SD per group, indicating the level of significance (* p < 0.05). ns: not significant. PGIIBU: groups with pulp damage treated with ibuprofen at 14 h. PGIDEX: groups with pulp damage treated with dexamethasone at 14 h. PGIRTX: experimental groups with pulp damage treated with resiniferatoxin at 14 h.
3. Discussion
The dental pulp and the periodontium are intrinsically related from their embryonic origin, and although both compartments usually present independent pathologies, there are connections that allow the passage of microorganisms between them. Thus, the disease of one tissue can affect the other and generate endo-periodontal lesions [35]. Diverse investigations have studied the relationship between the pulp and periodontal disease [36], demonstrating that there is a correlation between both diseases [37,38]. In this sense, endo-periodontal lesions correspond to clinical manifestations derived from the inflammatory and pathological interaction between the pulp and periodontal tissues, which occurs through communication structures such as the apical foramen, lateral canals, accessory canals and dentin tubules [39,40].
The pathogenesis of endodontic and periodontal lesions is determined by multiple factors, including the microbial burden, the diversity, and virulence of the pathogens, and the interactions they establish with each other [41]. In this context, inflammatory mediators present in pulp and periodontal tissues play a fundamental role in the immune response to the infectious environment. These mediators exert pleiotropic effects, including the activation of inflammatory leukocytes, modification of vascular permeability, and the induction of bone resorption processes [42,43,44,45]. In the present study, plasma levels of proinflammatory mediators (PGE2 and TNF-α) as well as histopathological parameters of gingival tissue were evaluated after pulp tissue damage in a murine experimental model treated with resiniferatoxin, which is discussed in depth and detail below.
Arachidonic acid (ARA) that is esterified at the inner surface of the cell membrane is hydrolyzed to its free form by phospholipase A2 (PLA2) [46], which can subsequently be metabolized by diverse enzymes, such as lipoxygenases (LOX), cytochrome P450 enzymes (CYP) and cyclooxygenases (COX), producing a wide variety of bioactive mediators [47]. There are two main isoforms of COX: the COX-1 isoform, which is constitutively expressed in most tissues, and the COX-2 isoform, which is induced during inflammatory processes triggered by various stimuli, such as cytokines and endotoxins [48]. In this sense, the production of PGE2, an endogenous lipid mediator of inflammation, is regulated by COX-2 [49]. PGE2 plays a key role in generating the inflammatory response, as its biosynthesis increases significantly in inflamed tissue and contributes to the development of the cardinal signs of acute inflammation, such as edema and redness, as well as fever and hyperalgesia [50].
Current scientific evidence suggests that PGE2 plays a key role in the pathogenesis of endo-periodontal lesions by modulating the local immune response and promoting tissue destruction. During pulp tissue inflammation, PGE2 has been reported to increase vascular permeability [51] and enhance the pain response [52]. In addition, PGE2 is capable of inhibiting the osteogenic differentiation of mesenchymal stem cells [53], but it also stimulates the expression of mineralization genes in undifferentiated pulp cells [12], promoting the formation of tertiary dentin [54]. Clinical studies have reported a significant increase in PGE2 in cases of reversible and irreversible pulpitis, compared to healthy pulp [55,56,57]. Similarly, preclinical studies (experimental models in rats) have reported a significant increase in PGE2 during pulp inflammation [58], showing positive immunoreactivity for PGE2 three days after pulp exposure [59]. Finally, in vitro assays with human pulp cells show that PGE2 levels increase 24 h after stimulation with IL-1β and TNF-α in a dose-dependent manner [60]. During inflammation of the gingival tissue, studies have reported an important role for PGE2, since oral pathogens and proinflammatory cytokines (such as TNF-α, IL-1α, IL-1β) induce the expression of COX-2 and, therefore, the production of PGE2 in gingival fibroblasts, amplifying local inflammation [61,62]. In this context, the overproduction of PGE2 in periodontal tissues promotes vasodilation, increases vascular permeability, and enhances pain perception, causing the clinical signs of inflammation [63,64,65]. In addition, the vasoactive effects of PGE2 are also enhanced by synergistic interactions with other inflammatory mediators such as bradykinin, the complement system, and histamine [66]. On the other hand, several studies have reported elevated levels of PGE2 in gingival crevicular fluid [67,68], saliva, inflamed periodontal tissues, periapical exudates, and active endodontic lesions, which have been positively correlated with bleeding on probing, attachment loss, tissue destruction, and bone loss, as well as with the clinical severity of the disease and acute symptoms in endo-periodontal lesions [11,63,64,65,69,70].
TNF-α is a cytokine with pleiotropic effects, produced by various types of immune cells, mainly T lymphocytes, activated macrophages, and natural killer cells. At the physiological level, TNF-α is an important component of the normal immune response, which is essential for the initiation and progression of the inflammatory response, through the stimulation of the recruitment and migration of immune cells to the site of inflammation, and promotion of the synthesis of other inflammatory molecules, such as interleukins and chemokines. However, overproduction or improper function of TNF-α can be harmful, causing chronic inflammation and tissue damage, leading to diverse diseases [71,72].
TNF-α plays a central role in the pathogenesis of endo-periodontal lesions [73,74], as it drives inflammation, immune cell recruitment, and bone resorption. In the case of pulp inflammation, TNF-α has been observed to play a protective role, because it promotes odontoblastic differentiation [75,76], inducing greater mineralization through an increase in proteins associated with the formation of reparative dentin [77]. Studies in human dental pulp have reported that gene expression (mRNA) [78,79,80] and protein synthesis [81,82,83] of TNF-α increase significantly in cases of reversible and irreversible pulpitis, compared to healthy pulps. Likewise, studies in experimental animal models have reported maximum TNF-α expression three hours after LPS stimulation in rats [84], and twelve hours after pulp damage in mice [85]. On the other hand, TNF-α plays a crucial and fundamental role in protecting against periodontal pathogens [86]. Studies in animal models suggest that TNF-α plays an important role in the pathogenesis of periodontal disease, in the transition from gingivitis to periodontitis [87,88]. Likewise, clinical studies have reported a significant increase in local levels of TNF-α in gingival tissue, gingival crevicular fluid, saliva and periapical tissues in patients with chronic and apical periodontitis, which correlates with disease severity and tissue deterioration [89,90,91,92]. This destruction of periodontal tissues by TNF-α is related to several of its actions [93]. On the one hand, TNF-α induces the recruitment of circulating leukocytes [94] and stimulates the production of other proinflammatory mediators, which sustains the inflammatory response, and promotes the release of tissue enzymes and matrix metalloproteinases (MMPs), thus reducing the reparative capacity of the periodontium [95,96,97,98] and amplifying bone resorption in endo-periodontal lesions [99,100]. On the other hand, TNF-α participates in the stimulation of the differentiation and activity of osteoclasts, osteoblasts and osteocytes, increasing the expression of the receptor activator of the NF-κB ligand (RANK) and macrophage colony-stimulating factor (M-CSF), which leads to greater bone resorption in inflamed periodontal and periapical tissues, enhancing bone loss during endo-periodontal lesions [101,102,103,104,105].
The scientific evidence mentioned above highlights the importance of the role of PGE2 and TNF-α during pulp and periodontal inflammation. Several experimental and clinical studies have reported that during periodontal diseases, plasma levels of both PGE2 [69,106,107] and TNF-α [108,109,110] increase significantly, indicating local and systemic inflammation. Regarding pulp inflammation, the scientific evidence (mentioned previously) available to date has only reported the detection of PGE2 and TNF-α at the pulp tissue level. In particular, an experimental study conducted in a rat model reported that TNF-α levels increased significantly at the pulp and systemic levels, ninety minutes after systemic exposure to lipopolysaccharide (LPS), but not due to pulp damage [111]. Similarly, there is currently no reported information on the detection of systemic levels of PGE2 and TNF-α in endo-periodontal lesions. In this context, the present study is relevant as it is the first to report the detection of systemic levels of PGE2 and TNF-α in an experimental model of gingival tissue inflammation in BALB/c mice, since it was observed that at 14 h after pulp damage, there was a significant increase (* p < 0.05) in plasma levels of TNF-α and an upward trend in plasma levels of PGE2 in the PGI group, compared to the control groups HCG and RTXHG. This finding is consistent with the literature, as a study in an experimental model of pulp inflammation in BALB/c mice reported that plasma levels of PGE2 and TNF-α increased significantly (* p < 0.05) at 14 h after pulp damage [34]. Together, these findings indicate that both PGE2 and TNF-α are key mediators of the pulp and gingival inflammatory response, participating in the amplification of inflammation. Importantly, systemic levels of PGE2 and TNF-α were not intended to serve as direct surrogates of local gingival inflammation, but rather as complementary indicators of overall inflammatory status in response to pharmacological intervention.
Currently, NSAIDs are widely used for the treatment of inflammation, pain and fever [112], through the blocking of COX isoenzymes (COX-1 and COX-2), inhibiting the production of prostaglandins (PG) and thromboxanes (Tx) [113]. Ibuprofen is one of the most prescribed and used NSAIDs [114] for its analgesic, anti-inflammatory and antipyretic properties [115,116], which has a wide therapeutic index, since at high doses (1800–2400 mg/day) it is used for the treatment of chronic inflammatory diseases, while at low doses (800–1200 mg/day) it is indicated for the relief of mild (dental) pain and inflammation [117].
Several experimental and clinical studies have demonstrated that ibuprofen significantly reduces PGE2 levels in inflamed oral tissues, both pulp and periodontal tissues (Table 1), primarily by inhibiting arachidonic acid metabolism and COX activity [118,119,120,121,122,123,124,125,126]. In animal models and patients with irreversible pulpitis, ibuprofen treatment was associated with a significant decrease in PGE2 in pulp tissues and pulp blood samples [118,121,122]. Similarly, in vitro studies, clinical trials, and animal models of periodontitis showed marked inhibition of PGE2 production in gingival tissues and gingival crevicular fluid, accompanied by a reduction in postoperative pain and inflammation [123,124,125,126]. In contrast, evidence regarding the effect of ibuprofen on TNF-α is limited and contradictory (Table 1). Although a significant increase in TNF-α has been described during endo-periodontal lesions, some studies did not observe a significant reduction after ibuprofen treatment [120,127,128]. However, other studies have reported a decrease in TNF-α in blood samples obtained from the pulp of patients with irreversible pulpitis and stimulated gingival epithelial cells [118], and in gingival epithelial cells stimulated with P. gingivalis-LPS [129]. Recently, a study showed that, in an experimental model of pulp inflammation, ibuprofen significantly decreased (* p < 0.05) plasma levels of PGE2 and TNF-α [34]. In accordance with these findings, the present study demonstrates that ibuprofen significantly reduces (p < 0.05) plasma levels of PGE2 and TNF-α during gingival inflammation 14 h after pulp damage, providing novel evidence in a murine model that integrates the pathophysiological context of endo-periodontal lesions. Furthermore, these effects could be related not only to COX inhibition, but also to the modulation of the NF-κB pathway and the production of pro-inflammatory cytokines, such as TNF-α, similar to steroid anti-inflammatory drugs such as glucocorticoids [130,131,132,133].
Table 1.
Evidence on the effects of ibuprofen on PGE2 and TNF-α in pulpal and periodontal tissues.
Glucocorticoids are potent steroidal anti-inflammatory drugs, widely used for the treatment of inflammatory diseases [134]. Their main mechanism of action is genomic, mediated by interaction with their nuclear receptor (GR) [135]. The binding of glucocorticoids with their receptor GR forms an active protein complex (GC-GR), which translocates to the cell nucleus and binds to promoter regions of target genes in DNA, called glucocorticoids response elements (GREs), regulating gene expression, either positively or negatively [136]. Positive regulation causes gene transcription and translation of anti-inflammatory proteins, while negative regulation occurs through the suppression of pro-inflammatory gene expression, inhibiting transcription factors such as NF-κB [29,137].
Dexamethasone is a synthetic glucocorticoid with potent anti-inflammatory and immunosuppressive properties, widely used to modulate the exacerbated inflammatory response [138]. In pulpal diseases, most studies have focused on its efficacy in controlling endodontic pain, particularly in inferior alveolar nerve blocks [139,140,141,142,143,144], with limited evidence on its direct effect on pulpal inflammation and PGE2 and TNF-α levels. However, recent studies have shown that dexamethasone, administered locally or systemically, reduces TNF-α expression, promotes dentin mineralization [145], and significantly decreases (* p < 0.05) plasma levels of PGE2 and TNF-α at the systemic level, following pulp damage in an experimental model of pulpal inflammation in mice [34] (Table 2). In the periodontal context, dexamethasone has shown preventive effects on postoperative pain [146] and marked anti-inflammatory activity in in vitro studies and animal models [147,148,149,150,151,152]. At the cellular level, dexamethasone inhibits the expression of microsomal prostaglandin E synthase-1 (mPGES-1) [153,154], COX-2 [155,156], as well as the production of PGE2 [157,158,159] and TNF-α [160,161] in human gingival fibroblasts (GHFs) and human periodontal ligament (PDL) cells [162], previously stimulated with pro-inflammatory mediators, such as IL-1β, TNF-α, bradykinin and LPS. In animal models, dexamethasone significantly inhibited the increase in TNF-α associated with periodontitis [163], and reduced periodontal inflammation and alveolar bone loss, although alterations in mineral density and increased bone porosity have also been described [164,165,166,167] (Table 2). In accordance with this evidence, the present study demonstrates for the first time that dexamethasone significantly reduces (* p < 0.05) systemic levels of PGE2 and TNF-α during gingival inflammation 14 h after the pulp damage in a murine model, providing novel evidence in the pathophysiological context of endo-periodontal lesions.
Table 2.
Evidence on the effects of dexamethasone on pulp and periodontal inflammation.
Regarding dexamethasone, its prolonged therapeutic use can suppress the local immune response, delay healing, and promote secondary infections [145,168]. Systemic treatment or high doses alter the function of pulp cells and reduce the number of osteoblasts and osteoclasts, affecting bone repair and mineral density, with an impact on tissue homeostasis [169,170]. Furthermore, chronic therapeutic use of dexamethasone can cause gingival ulceration, attachment loss, periodontal fiber alterations, and alveolar bone loss, due in part to the inhibition of fibroblast activity and collagen formation, which delays tissue repair and promotes local osteoporosis [170,171]. In addition, the immunosuppression associated with dexamethasone can exacerbate periodontitis and induce spontaneous alveolar bone loss, especially at high doses [166]. At a systemic level, prolonged treatment with dexamethasone has been associated with delayed wound healing, increased risk of infection, mild hyperglycemia, and osteoporosis [141,172,173,174,175,176,177].
Currently, there is a wide variety of anti-inflammatory agents available [30]. However, given the limited therapeutic use of ibuprofen and dexamethasone in pulpal and gingival inflammation, there is still a need to develop new therapeutic alternatives that contribute to the treatment of inflammation in dental practice, in particular, through the use of biological products, such as resiniferatoxin. In addition to resiniferatoxin acting as a molecular analgesic by desensitizing nerves that express TRPV1 [178], several studies have shown that resiniferatoxin has a significant anti-inflammatory activity or effect. In vitro studies have reported that resiniferatoxin was capable of inhibiting NF-κB expression in a dose-dependent manner in the human leukemic myelomonoblastic (ML-1a) cell line stimulated with TNF-α [179], as well as iNOS and COX-2 expression in RAW264.7 macrophages stimulated with LPS and IFN-γ, resulting in a decrease in PGE2 and NO [180]. On the other hand, in vivo studies in models of ischemic acute renal failure (ARF) [181], Trichinella spiralis infection [182,183,184,185], and LPS-induced inflammation have demonstrated the anti-inflammatory and immunomodulatory effects of resiniferatoxin, which significantly reduced levels of pro-inflammatory mediators such as TNF-α, NO, PGE2, IL-12, IFN-γ and IL-1β, while increasing anti-inflammatory cytokines such as IL-10, IL-4, and IL-13, possibly through the NF-κB signaling pathway, independent of TRPV-1 receptors [33]. Another study evaluated the effect of resiniferatoxin in a murine model with LPS-induced inflammation. It was observed that treatment with resiniferatoxin significantly reduced plasma levels of PGE2, NO, IL-1β and TNF-α. In addition, Bay 11-7082 and CPZ combined with resiniferatoxin showed a synergistic effect, decreasing inflammatory markers. These findings suggest that the anti-inflammatory effect of resiniferatoxin is apparently associated with the NF-κB signaling pathway, independent of TRPV-1 receptors [33]. However, this is the first report indicating that resiniferatoxin treatment decreases the systemic production of these proinflammatory mediators during gingival tissue inflammation after pulp damage in a murine experimental model.
Periodontal lesions are characterized by an increase in neutrophils, which, through the release of chemokines, promote the recruitment and activation of immune cells, as well as osteoclastic bone resorption, contributing to both the onset and progression of periodontitis [186]. In addition, macrophages represent a relevant source of pro-inflammatory mediators such as IL-1β, TNF-α, MMP and PGE2, whose elevated levels in gingival tissue and CGF are directly associated with the severity of periodontal disease [187]. Similarly, chronic pulp inflammation is characterized by inflammatory infiltrate, fibrosis, and progressive tissue deterioration, which can culminate in pulp necrosis and loss of defensive function [188]. A study of an experimental model of pulp inflammation in mice showed that 14 h after pulp damage, there was a mild infiltrate of inflammatory cells, presence of edema, vascular leakage, and necrosis of the pulp tissue, while 18 h after pulp damage, a significant increase in the infiltrate of inflammatory cells to moderate was observed, with the presence of edema, vascular leakage, and no pulp necrosis [34]. Histopathological evidence indicates that periodontitis can induce inflammation, fibrosis, and pulp necrosis, confirming the close interrelationship between gingival and pulp inflammation [189]. In our study, it was observed that, 14 h after pulp damage, there was a significant increase (* p < 0.05) in the chronic infiltrate of inflammatory cells. Furthermore, when treatments with IBU and dexamethasone were administered, it was observed that 14 h after pulpal damage, the inflammatory cell infiltrate decreased significantly, presenting a mild focal inflammatory process. Our results are consistent with what has been reported in the literature, as it was observed that when treatment with ibuprofen, dexamethasone and resiniferatoxin was administered, it significantly reduced the number of cells infiltrated in the pulp tissue, but with the presence of edema, vascular leakage and pulp necrosis [34]. This reduction in the observed inflammatory infiltrate is due to the fact that GCs such as dexamethasone are capable of inducing apoptosis in immune system cells [190,191,192], inhibiting chemotaxis [193] and cell proliferation [194]. In the case of ibuprofen, it has also been observed that it is capable of inhibiting cell proliferation [132]; however, further studies are needed to confirm this hypothesis. Although the inflammatory infiltrate likely comprises a mixture of mononuclear and polymorphonuclear cells, the histological assessment was limited to quantification of total inflammatory cell infiltration using hematoxylin and eosin staining, without cell-type-specific identification. Future studies incorporating cell-specific markers or immunohistochemical approaches, such as myeloperoxidase staining, may further refine characterization of inflammatory cell populations.
Regarding resiniferatoxin, studies in rat models with T. spiralis infection have reported that resiniferatoxin treatment significantly reduced plasma and intestinal eosinophils. [182,183,184,185]. Furthermore, when treatment with resiniferatoxin was administered, in a study of an experimental model of pulp inflammation in mice, it was observed that 14 h after pulpal damage, the inflammatory cell infiltrate significantly decreased necrosis [34]. These findings are consistent with our results, as this is the first study to show that resiniferatoxin treatment is capable of reducing the number of inflammatory cells infiltrated in the gingival tissue, 14 h after pulp damage. Although there is no clear evidence of the mechanisms by which resiniferatoxin presents this effect, our hypothesis is based on the fact that this effect of resiniferatoxin could be associated with its ability to negatively regulate the production of proinflammatory mediators, since the survival of inflammatory cells is associated with the production of proinflammatory cytokines [195,196]. However, more studies are needed to confirm this hypothesis. Accordingly, while pulp inflammation represents the initiating event, the present study specifically addresses the downstream gingival inflammatory response, providing novel evidence of the systemic and periodontal anti-inflammatory effects of resiniferatoxin. Although resiniferatoxin is known to interact with sensory neurons, the present study was not designed to investigate the neural mechanisms underlying its anti-inflammatory effects, which remain an important subject for future investigation.
Resiniferatoxin has become a potent analgesic and anti-inflammatory compound due to its high affinity for TRPV-1 receptors and its ability to induce long-lasting desensitization of nociceptive neurons [197]. In addition to its neuromodulatory effects, increasing evidence suggests that resiniferatoxin exerts immunomodulatory actions by inhibiting NF-κB signaling and suppressing the production of pro-inflammatory mediators, such as PGE2 and TNF-α. These mechanisms could explain the significant reduction in these inflammatory mediators at the systemic level and in the gingival inflammatory infiltrate observed in the present study. In this context, when comparing the anti-inflammatory effect of the three treatments with ibuprofen, dexamethasone, and resiniferatoxin in the present study, no statistically significant differences were observed in plasma levels of PGE2 and TNF-α, showing a similar anti-inflammatory effect 14 h after pulp damage. Histologically, 14 h after pulp damage, a greater anti-inflammatory effect was observed with the ibuprofen and dexamethasone treatments compared to the resiniferatoxin treatment; however, all three treatments showed a significant reduction in inflammatory infiltrate. Our findings are consistent with previous reports, as various experimental studies in animal models have shown that resiniferatoxin has a similar anti-inflammatory effect to treatment with other anti-inflammatory drugs such as ibuprofen and dexamethasone, at a lower therapeutic dose, demonstrating efficacy and pharmacological potency [33,34,183,184,185]. However, despite its promising anti-inflammatory properties, the therapeutic use of resiniferatoxin is not without potential limitations. At high doses or with inappropriate routes of administration [198], resiniferatoxin treatment has been reported to be associated with cytotoxic effects, neuronal degeneration, and prolonged sensory deficits due to excessive calcium influx mediated by TRPV-1 [199,200]. Furthermore, resiniferatoxin-induced neurotoxicity and localized tissue damage have been described in some experimental models [201,202,203,204]. High doses of resiniferatoxin have also been reported to cause severe inflammation of the digestive mucosa, gastroenteritis, abdominal pain, vomiting, hematuria, arrhythmia, pulsatile seizures, and death by asphyxiation [205], highlighting the importance of dose optimization, controlled delivery systems, and careful evaluation of safety profiles. Alternative routes of administration, including localized delivery, represent an important area for future investigation but were beyond the scope of the present systemic pharmacological evaluation. Therefore, while resiniferatoxin represents a promising alternative to conventional anti-inflammatory drugs, further preclinical studies are required to define its therapeutic window, long-term safety, and optimal administration strategies before its translation into dental clinical applications.
Study Limitations and Future Directions
This study has several limitations that should be acknowledged. First, the experimental model was intentionally designed to evaluate pulp–gingival inflammation induced by controlled mechanical pulp exposure, allowing isolation of this specific stimulus. Accordingly, the findings should be interpreted within the context of a mechanical injury model rather than as a comprehensive representation of all etiological factors associated with endo-periodontal injuries. Other etiological stimuli, including thermal, microbiological, chemical, or caries-driven models, may activate distinct inflammatory pathways and warrant investigation in future studies.
Second, although pulpal damage served as the initiating stimulus, histopathological analyzes were focused on gingival tissue in accordance with the primary objective of the study. Pulpal inflammatory changes following mechanical injury and resiniferatoxin treatment have been previously characterized [34] and were therefore not reassessed. In addition, systemic inflammatory mediators were prioritized as outcome measures to capture the overall inflammatory response. Future studies incorporating simultaneous pulp and gingival tissue analysis, as well as tissue-specific transcriptional profiling, may provide further mechanistic insight.
The inflammatory response to pulp exposure is dynamic and evolves over time. In this study, a 14 h time point was selected to assess early systemic and gingival inflammatory responses based on prior evidence. While appropriate for evaluating acute pharmacological modulation, additional time points (24–72 h), as reported in other murine models [85], would be valuable to characterize temporal progression and longer-term effects.
No postoperative analgesia was administered to avoid pharmacological interference with inflammatory pathways. While this may have contributed to elevated baseline systemic inflammatory mediators, all experimental groups were exposed to identical nociceptive conditions, allowing relative comparisons between treatments to remain interpretable. It should be noted that anti-inflammatory treatments were administered after the inflammatory response was established; therefore, the present study evaluates the acute pharmacological modulation of an ongoing pulp–gingival inflammatory process rather than the prevention or early development of inflammation. Additionally, because treatments were administered systemically, changes in circulating inflammatory mediators may reflect effects beyond the gingival lesion itself, including systemic or off-target pharmacological actions.
Finally, although animals were homogeneous and standardized procedures, formal randomization, blinding, and a priori power calculations were not implemented. While the sample size (n = 6 per group) was sufficient to detect statistically significant differences in this exploratory study, these methodological refinements should be incorporated in future confirmatory investigations to further strengthen rigor and reduce the risk of type II errors.
4. Materials and Methods
4.1. Experimental Animal Model
Male BALB/c mice of two and a half months of age, with an average body weight of 25 g, were used. Six groups of six mice each were formed: a healthy control group (HCG); a healthy group treated with resiniferatoxin (RTXHG); a control group with pulp–gingival inflammation at 14 h (PGI); a pharmacological comparator group with pulp–gingival inflammation and treated with ibuprofen at 14 h (PGIIBU); a pharmacological comparator group with pulp–gingival inflammation and treated with dexamethasone at 14 h (PGIDEX); and an experimental group with pulp–gingival inflammation and treated with resiniferatoxin at 14 h (PGIRTX). Animals were assigned to experimental groups based on predefined experimental design (animals used were homogeneous in terms of strain, sex, age, and weight); however, no formal randomization or blinding procedures were applied. This study was reviewed and approved by the Bioethics Committee of the Health Sciences Area of the Autonomous University of Zacatecas, with the bioethical approval number ACS/UAZ/083/2019 and was made in accordance with the Official Mexican Norm (NOM-062-ZOO-1999), published by the Secretariat of Agriculture, Livestock, Rural Development, Fisheries and Food (SAGARPA) in the Official Gazette of the Federation (México) on 28 June 2001.
4.2. Induction of Pulp Lesion
Pulp lesion was performed according to previously published methods (Figure 1a,b, in Section 2 of results) [34,85]. The dental cavities of the PGI, PGIIBU, PGIDEX, and PGIRTX groups were prepared on the occlusal surface of the bilateral upper first molars (class 1 cavity), with a #1/4 dental round bur, under a surgical microscope (40×). The upper first molars were drilled using a dental micromotor at approximately 20,000–30,000 rpm with a cooling system, until the pulp was observed through the transparency of the dentin floor of the cavity. Pulp exposure was performed using an endodontic hand file (0.15 mm diameter tip, 2% taper), gently inserted approximately 1–1.5 mm into the pulp chamber, performing 2–3 controlled strokes over a period of 5–10 s, avoiding excessive pressure to standardize the extent of mechanical damage, leaving the cavity open and exposed to the oral environment. Subsequently, it was determined whether the pulp lesion induced damage (inflammation) in gingival tissue (see gingival histopathology).
4.3. Drug Treatment
4.3.1. Anesthetic Treatment
All mice were anesthetized with sodium pentobarbital (PISABENTAL®, Reg. SAGARPA Q-7833-215) with a dose of 50 mg/Kg, administered intraperitoneally. Anesthesia was performed thirty minutes before pulp lesion. For plasma collection performed 14 h later, animals were re-anesthetized thirty minutes before the procedure [34]. All experimental procedures were conducted in accordance with the ethical guidelines established by the Institutional Bioethics Committee and the Official Mexican Norm (NOM-062-ZOO-1999). Animals were anesthetized with sodium pentobarbital prior to pulp exposure to minimize pain during the procedure. After the intervention, mice were closely monitored for signs of distress, including changes in posture, locomotion, grooming behavior, food and water intake, and response to external stimuli. Humane endpoints were predefined, and animals exhibiting severe or persistent signs of pain, distress, infection, or systemic deterioration were humanely euthanized with an anesthetic overdose, in accordance with institutional protocols. No unexpected morbidity or mortality was observed during the experimental period. Following recovery from anesthesia, animals were monitored for general wellbeing and behavior. All mice regained normal posture and mobility, and exhibited typical behaviors including ambulation, feeding, and grooming. No overt signs of distress or impaired activity were observed prior to sample collection.
4.3.2. Anti-Inflammatory Treatment
The PGIIBU group was treated with commercial ibuprofen, administered orally with a dose of 90 mg/Kg [34,206], thirty minutes before plasma collection at 14 h. The PGIDEX group was treated with commercial dexamethasone sodium phosphate, administered intraperitoneally with a dose of 1 mg/Kg [34,182], ninety minutes before plasma collection at 14 h.
4.3.3. Treatment with Resiniferatoxin
The control group RTXHG and experimental PGIRTX group were treated with resiniferatoxin (Sigma-Aldrich, 3050 Spruce St., Saint Louis, MO, USA, 63103), administered intraperitoneally [33,34] with a dose of 20 μg/Kg, ninety minutes before plasma collection at 14 h.
4.4. Plasma Collection
All the mice were administered 200 IU of heparin subcutaneously and fifteen minutes later the blood was obtained by the cardiac puncture method. For plasma collection, animals were re-anesthetized under deep anesthesia prior to cardiac puncture. Blood collection was performed as a terminal procedure, in accordance with institutional ethical guidelines and the Official Mexican Norm NOM-062-ZOO-1999. The blood was centrifuged for ten minutes at 10,000 rpm, and then the plasma was collected. After, aliquots of 60 μL were taken and deposited in Eppendorf tubes and stored at −80 °C until use.
4.5. Quantification of PGE2 and TNF-α in Plasma
Plasma samples from the HCG group were collected at the same experimental time point as those from the RTXHG group; the only difference between groups was the administration of resiniferatoxin to the RTXHG group 90 min prior to sampling, then the concentrations of PGE2 and TNF-α in plasma were determined. In the PGI, group, the plasma was collected at 14 h after that pulp–gingival lesion, then the concentrations of PGE2 and TNF-α were determined. Whereas, in the PGIIBU, PGIDEX, and PGIRTX groups, the plasma was collected at 14 h after pulp–gingival lesion, and then the concentrations of PGE2 and TNF-α were determined. Plasma levels of PGE2 were determined by ELISA using Mouse Prostaglandin E2 (PGE2) ELISA Kit, MyBioSource, San Diego, CA, USA. Plasma levels of TNF-α were determined by ELISA using Mouse TNF-alpha DuoSet® ELISA, R&D Systems, Inc. a Bio-Techne Brand USA (Minneapolis, MN, USA). Plasma samples were analyzed in duplicate and diluted 1:2 when necessary. Standard curves were generated for each assay by serial dilutions of the provided standards, covering a concentration range of 7.8–500 pg/mL for PGE2, and 31.3–2000 pg/mL for TNF-α. Absorbance was measured using a microplate reader (450 nm), and cytokine concentrations were calculated based on the corresponding standard curves (Figure 1b, in Section 2 of results).
4.6. Histopathological Analysis
Although pulp tissue samples were obtained during tissue processing, the histopathological and quantitative analyses in this study focused exclusively on gingival tissue to assess periodontal inflammation secondary to pulp damage. This was because our group had already reported inflammatory changes in pulp tissue following mechanical damage and resiniferatoxin treatment [34], and therefore these were not included in the present analysis. For histopathological analysis of the gingival tissue, attached gingiva was removed from the first upper molars, fixed in 4% paraformaldehyde (PFA) in PBS at 4 °C for 24 h, and embedded in paraffin wax. Paraffin-embedded gingival tissues were sectioned at a thickness of 4–5 μm using a rotary microtome. Sections were obtained in a bucco–lingual orientation to ensure consistent anatomical evaluation. For each specimen, three non-consecutive levels were analyzed, with multiple sections examined per level to assess tissue architecture and inflammatory infiltrate. Subsequently, sections were cut and stained with H&E on a glass microscope slide [34].
Gingival tissue integrity and damage were evaluated based on the following histopathological criteria: (1) location of inflammatory cells (absent, restricted to the exposed site, limited to the gingival epithelium, or extending throughout the gingival connective tissue); (2) intensity of the inflammatory infiltrate (baseline: 0–20 inflammatory cells; mild: 21–40 inflammatory cells; moderate: 41–80 inflammatory cells; severe: over 80 inflammatory cells); and (3) inflammatory edema (absent and present). The inflammatory cells infiltrated into the gingival tissue were counted in 10 randomly selected microscopic fields per sample, analyzed in triplicate using a 40× objective, covering a total analyzed area of approximately 1.0 mm2. The results were expressed as the number of infiltrated inflammatory cells IIC/TAU (Tissue Area Unit: 1 mm2). The histopathological criteria were evaluated under optical light microscope (Carl Zeiss Primo Star microscope Carl Zeiss Microscopy GmgH 37081 Gottingen, Germany, model 3708) with objectives 10× and 40× [34,85]. Histological scoring was performed in a blinded manner by a trained observer using predefined criteria.
4.7. Statistical Analysis
Results are presented as mean ± standard deviation (SD). To minimize Type I errors (false positives), a predefined significance level (* p < 0.05) was applied, and comparisons between groups were performed using a one-way ANOVA, suitable for controlling for overall variance across multiple groups. Regarding Type II errors (false negatives), the use of standardized experimental conditions, homogeneous animal populations, and effect sizes consistent with previous studies increased the likelihood of detecting biologically relevant differences, despite the limited sample size. When significant differences were detected, Tukey’s post hoc test was applied for multiple comparisons. Normality was assessed using the Shapiro–Wilk test, and homogeneity of variances was evaluated using Levene’s test. All datasets satisfied the assumptions of normality and homogeneity of variance required for parametric analysis. Statistical analyses were performed in GraphPad PRISM for Mac version 10 (GraphPad Software, San Diego, CA, USA).
5. Conclusions
In this study, systemic levels of proinflammatory mediators, including PGE2 and TNF-α, were detected during gingival inflammation following mechanical pulp damage in a murine experimental model. In addition, resiniferatoxin exhibited an anti-inflammatory effect, evidenced by significant reductions in plasma PGE2 and TNF-α levels, as well as decreased inflammatory cell infiltration in gingival tissue, with effects comparable to those observed with ibuprofen and dexamethasone. Within the constraints of this controlled preclinical model and the acute time window evaluated, these findings suggest that resiniferatoxin represents a promising experimental anti-inflammatory approach for modulating gingival inflammation secondary to pulp injury, warranting further investigation in complementary models and temporal settings.
Author Contributions
Conceptualization, J.L.M.-C., O.G.-C., G.S.C.-C., and J.J.B.; writing—original draft preparation, J.L.M.-C., O.G.-C., G.S.C.-C., and J.J.B.; specialized and systematic search, and writing, J.L.M.-C., O.G.-C., G.S.C.-C., P.T.V.-G., F.C.-R., M.I.C.-R., M.A.L.-L., O.R.-L., and J.J.B.; design and elaboration of figures, J.L.M.-C., O.G.-C. and J.J.B.; writing—review and editing, J.L.M.-C., O.G.-C., G.S.C.-C., P.T.V.-G., F.C.-R., M.I.C.-R., M.A.L.-L., O.R.-L., and J.J.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was reviewed and approved by the Bioethics Committee of the Health Sciences Area of the Autonomous University of Zacatecas, with the bioethical approval number ACS/UAZ/083/2019, on 14 October 2019 and was made in accordance with the Official Mexican Norm (NOM-062-ZOO-1999), published by the Secretariat of Agriculture, Livestock, Rural Development, Fisheries and Food (SAGARPA) in the Official Gazette of the Federation (México) on 28 June 2001.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding authors.
Acknowledgments
The first and corresponding author thanks the other authors for their collaboration in this work.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Muñoz-Carrillo, J.L.; Vázquez-Alcaraz, S.J.; Vargas-Barbosa, J.M.; Ramos-Gracia, L.G.; Alvarez-Barreto, I.; Medina-Quiroz, A.; Díaz-Huerta, K.K. The Role of Micrornas in Pulp Inflammation. Cells 2021, 10, 2142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, S.H.; Ye, L.; Love, R.M.; Farges, J.C.; Yumoto, H. Inflammation of the Dental Pulp. Mediat. Inflamm. 2015, 2015, 980196. [Google Scholar] [CrossRef] [Scilit]
- Cooper, P.R.; Holder, M.J.; Smith, A.J. Inflammation and Regeneration in the Dentin-Pulp Complex: A Double-Edged Sword. J. Endod. 2014, 40, S46–S51. [Google Scholar] [CrossRef] [Scilit]
- Shah, D.; Lynd, T.; Ho, D.; Chen, J.; Vines, J.; Jung, H.D.; Kim, J.H.; Zhang, P.; Wu, H.; Jun, H.W.; et al. Pulp–Dentin Tissue Healing Response: A Discussion of Current Biomedical Approaches. J. Clin. Med. 2020, 9, 434. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zanini, M.; Meyer, E.; Simon, S. Pulp Inflammation Diagnosis from Clinical to Inflammatory Mediators: A Systematic Review. J. Endod. 2017, 43, 1033–1051. [Google Scholar] [CrossRef] [Scilit]
- Winter, G.B.; Kramer, I.R.H. Changes in Periodontal Membrane and Bone Following Experimental Pulpal Injury in Deciduous Molar Teeth in Kittens. Arch. Oral Biol. 1965, 10, 279–289. [Google Scholar] [CrossRef] [Scilit]
- Bender, I.B.; Seltzer, S. The Effect of Periodontal Disease on the Pulp. Oral Surg. Oral Med. Oral Pathol. 1972, 33, 458–474. [Google Scholar] [CrossRef] [Scilit]
- Herrera, D.; Retamal-Valdes, B.; Alonso, B.; Feres, M. Acute Periodontal Lesions (Periodontal Abscesses and Necrotizing Periodontal Diseases) and Endo-Periodontal Lesions. J. Periodontol. 2018, 89, S85–S102. [Google Scholar] [CrossRef] [Scilit]
- Jivoinovici, R.; Suciu, I.; Dimitriu, B.; Perlea, P.; Bartok, R.; Malita, M.; Ionescu, C. Endo-Periodontal Lesion—Endodontic Approach. J. Med. Life 2014, 7, 542. [Google Scholar]
- Rotstein, I. Interaction between Endodontics and Periodontics. Periodontology 2000 2017, 74, 11–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sánchez, G.A.; Miozza, V.A.; Delgado, A.; Busch, L. Salivary IL-1β and PGE2 as Biomarkers of Periodontal Status, before and after Periodontal Treatment. J. Clin. Periodontol. 2013, 40, 1112–1117. [Google Scholar] [CrossRef] [Scilit]
- Lorencetti-Silva, F.; Pereira, P.A.T.; Meirelles, A.F.G.; Faccioli, L.H.; Paula-Silva, F.W.G. Prostaglandin E2 Induces Expression of Mineralization Genes by Undifferentiated Dental Pulp Cells. Braz. Dent. J. 2019, 30, 201–207. [Google Scholar] [CrossRef] [Scilit]
- Sy, K.; Chevalier, C.; Maton, M.; Mokbel, I.; Mahieux, S.; Houcke, I.; Neut, C.; Grosgogeat, B.; Deveaux, E.; Gritsch, K.; et al. Therapeutic Potential of Chlorhexidine-Loaded Calcium Hydroxide-Based Intracanal Medications in Endo-Periodontal Lesions: An Ex Vivo and In Vitro Study. Antibiotics 2023, 12, 1416. [Google Scholar] [CrossRef] [Scilit]
- Tewari, S.; Sharma, G.; Tewari, S.; Mittal, S.; Bansal, S. Effect of Immediate Periodontal Surgical Treatment on Periodontal Healing in Combined Endodontic–Periodontal Lesions with Communication—A Randomized Clinical Trial. J. Oral Biol. Craniofacial Res. 2018, 8, 105–112. [Google Scholar] [CrossRef] [Scilit]
- Nešković, J.; Živković, S. Possibilities of Endodontic Therapy of Endodonic-Periodontal Lesions. Srp. Arh. Celok. Lek. 2009, 137, 351–356. [Google Scholar] [CrossRef] [Scilit]
- Schmidt, J.C.; Walter, C.; Amato, M.; Weiger, R. Treatment of Periodontal-Endodontic Lesions—A Systematic Review. J. Clin. Periodontol. 2014, 41, 779–790. [Google Scholar] [CrossRef] [Scilit]
- García-Tuñón-Pérez, P.; Fernández-Jiménez, A.; Lafuente-Ibañez-de-Mendoza, I.; Estefanía-Fresco, R.; Marichalar-Mendia, X.; García-De-La-Fuente, A.M. Endoperiodontal Lesions: Diagnosis First, Then Treatment and Not Always Tooth Extraction: A Cross-Sectional Survey in Spain and a Proposal of a Clinical Treatment Protocol. J. Clin. Exp. Dent. 2024, 16, e32–e41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gomes, B.P.F.A.; Montagner, F.; Berber, V.B.; Zaia, A.A.; Ferraz, C.C.R.; de Almeida, J.F.A.; Souza-Filho, F.J. Antimicrobial Action of Intracanal Medicaments on the External Root Surface. J. Dent. 2009, 37, 76–81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raheja, J.; Tewari, S.; Tewari, S.; Duhan, J. Evaluation of Efficacy of Chlorhexidine Intracanal Medicament on the Periodontal Healing of Concomitant Endodontic-Periodontal Lesions Without Communication: An Interventional Study. J. Periodontol. 2014, 85, 1019–1026. [Google Scholar] [CrossRef] [Scilit]
- Shao, W.; Xiao, F.; Xu, Z.X.; Ren, R.H.; Wang, Y.; Wu, Y.Q. Treatment of Severe Periodontic-Endodontic Combined Lesions with Minocycline Hydrochloride Ointment Combined with Mineral Trioxide Aggregate. Exp. Ther. Med. 2018, 16, 1389–1396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abad, S.B.; Miranda, H.D.G.; Añaños, J.F.H. Manejo Farmacológico Coadyuvante Al Tratamiento Endodóntico. Rev. Estomatológica Hered. 2011, 21, 110–115. [Google Scholar] [CrossRef] [Scilit]
- Yadav, D.; Abhilash, A.; Mani, E.S.; Hari, K.; Arya, A. Clinical Efficacy of Locally Delivered Antibiotics in Treating Endodontic-Periodontal Lesions. J. Pharm. Bioallied Sci. 2025, 17, S1767–S1769. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aras, H.; Çağlayan, F.; Güncü, G.N.; Berberoğlu, A.; Kılınç, K. Effect of Systemically Administered Naproxen Sodium on Clinical Parameters and Myeloperoxidase and Elastase-Like Activity Levels in Gingival Crevicular Fluid. J. Periodontol. 2007, 78, 868–873. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beca, T.; Hernández, G.; Bascones, A. AINEs Como Tratamiento Coadyuvante de La Enfermedad Periodontal. Av. Periodoncia Implant. Oral 2007, 19, 101–113. [Google Scholar] [CrossRef] [Scilit]
- Holland, G.R. Steroids Reduce the Periapical Inflammatory and Neural Changes after Pulpectomy. J. Endod. 1996, 22, 455–458. [Google Scholar] [CrossRef] [Scilit]
- Marshall, J.G. Consideration of Steroids for Endodontic Pain. Endod. Top. 2002, 3, 41–51. [Google Scholar] [CrossRef] [Scilit]
- Wirth, T.; Lafforgue, P.; Pham, T. NSAID: Current Limits to Prescription. Jt. Bone Spine 2024, 91, 105685. [Google Scholar] [CrossRef] [Scilit]
- Cai, W.X.; Ma, L.; Zheng, L.W.; Kruse-Gujer, A.; Stübinger, S.; Lang, N.P.; Zwahlen, R.A. Influence of Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) on Osseointegration of Dental Implants in Rabbit Calvaria. Clin. Oral Implants Res. 2015, 26, 478–483. [Google Scholar] [CrossRef] [Scilit]
- Muñoz-Carrillo, J.L.; Muñoz-López, J.L.; Muñoz-Escobedo, J.J.; Maldonado-Tapia, C.; Gutiérrez-Coronado, O.; Contreras-Cordero, J.F.; Moreno-García, M.A. Therapeutic Effects of Resiniferatoxin Related with Immunological Responses for Intestinal Inflammation in Trichinellosis. Korean J. Parasitol. 2017, 55, 587–599. [Google Scholar] [CrossRef] [Scilit]
- Dinarello, C.A. Anti-Inflammatory Agents: Present and Future. Cell 2010, 140, 935–950. [Google Scholar] [CrossRef] [Scilit]
- Lee, Y.H.; Im, S.A.; Kim, J.W.; Lee, C.K. Vanilloid Receptor 1 Agonists, Capsaicin and Resiniferatoxin, Enhance MHC Class i-Restricted Viral Antigen Presentation in Virus-Infected Dendritic Cells. Immune Netw. 2016, 16, 233–241. [Google Scholar] [CrossRef] [Scilit]
- Szallasi, A. Resiniferatoxin: Nature’s Precision Medicine to Silence TRPV1-Positive Afferents. Int. J. Mol. Sci. 2023, 24, 15042. [Google Scholar] [CrossRef] [Scilit]
- Muñoz-Carrillo, J.L.; Villalobos-Gutiérrez, P.T.; Puebla-Pérez, A.M.; López-Luna, A.; La Torre, J.A.F.-D.; Alvarez-Barreto, I.; Gutiérrez-Coronado, O. El Tratamiento Con Resiniferatoxina Exhibe Propiedades Antiinflamatorias En Un Modelo Murino de Inflamación Inducida Por Lipopolisacárido. Rev. Biomed. 2021, 32, 137–146. [Google Scholar] [CrossRef] [Scilit]
- Muñoz-Carrillo, J.L.; Vargas-Barboza, J.M.; Villalobos-Gutiérrez, P.T.; Flores-De La Torre, J.A.; Vazquez-Alcaraz, S.J.; Gutiérrez-Coronado, O. Effect of Treatment with Resiniferatoxin in an Experimental Model of Pulpal Inflammatory in Mice. Int. Endod. J. 2021, 54, 2099–2112. [Google Scholar] [CrossRef] [Scilit]
- Al-Sibassi, A.; Niazi, S.A.; Clarke, P.; Adeyemi, A. Management of the Endodontic-Periodontal Lesion. Br. Dent. J. 2025, 238, 536–544. [Google Scholar] [CrossRef] [Scilit]
- Simring, M.; Goldberg, M. The Pulpal Pocket Approach: Retrograde Periodontitis. J. Periodontol. 1964, 35, 22–48. [Google Scholar] [CrossRef] [Scilit]
- Mazur, B.; Massler, M. Influence of Periodontal Disease on the Dental Pulp. Oral Surg. Oral Med. Oral Pathol. 1964, 17, 592–603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bergenholtz, G. Endodontics and Periodontics. In Clinical Periodontology and Implant Dentistry, 3rd ed.; Lindhe, J., Karring, T., Lang, N.P., Eds.; Munksgaard: Copenhagen, Denmark, 1997; pp. 296–331. [Google Scholar]
- Meng, H.X. Periodontic-Endodontic Lesions. Ann. Periodontol. 1999, 4, 84–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rupf, S.; Kannengießer, S.; Merte, K.; Pfister, W.; Sigusch, B.; Eschrich, K. Comparison of Profiles of Key Periodontal Pathogens in Periodontium and Endodontium. Dent. Traumatol. 2000, 16, 269–275. [Google Scholar] [CrossRef] [Scilit]
- Barbosa-Ribeiro, M.; De-Jesus-Soares, A.; Zaia, A.A.; Ferraz, C.C.R.; Almeida, J.F.A.; Gomes, B.P.F.A. Quantification of Lipoteichoic Acid Contents and Cultivable Bacteria at the Different Phases of the Endodontic Retreatment. J. Endod. 2016, 42, 552–556. [Google Scholar] [CrossRef] [Scilit]
- Artese, L.; Piattelli, A.; Quaranta, M.; Colasante, A.; Musani, P. Immunoreactivity for Interleukin 1β and Tumor Necrosis Factor-α and Ultrastructural Features of Monocytes/Macrophages in Periapical Granulomas. J. Endod. 1991, 17, 483–487. [Google Scholar] [CrossRef] [Scilit]
- Stashenko, P.; Jandinski, J.J.; Fujiyoshi, P.; Rynar, J.; Socransky, S.S. Tissue Levels of Bone Resorptive Cytokines in Periodontal Disease. J. Periodontol. 1991, 62, 504–509. [Google Scholar] [CrossRef] [Scilit]
- Martinho, F.C.; Chiesa, W.M.M.; Leite, F.R.M.; Cirelli, J.A.; Gomes, B.P.F.A. Antigenic Activity of Bacterial Endodontic Contents from Primary Root Canal Infection with Periapical Lesions against Macrophage in the Release of Interleukin-1β and Tumor Necrosis Factor α. J. Endod. 2010, 36, 1467–1474. [Google Scholar] [CrossRef] [Scilit]
- Graves, D.T.; Oates, T.; Garlet, G.P. Review of Osteoimmunology and the Host Response in Endodontic and Periodontal Lesions. J. Oral Microbiol. 2011, 3, 5304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yui, K.; Imataka, G.; Ichihashi, M. Prostaglandins: Biological Action, Therapeutic Aspects, and Pathophysiology of Autism Spectrum Disorders. Curr. Issues Mol. Biol. 2025, 47, 71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, B.; Wu, L.; Chen, J.; Dong, L.; Chen, C.; Wen, Z.; Hu, J.; Fleming, I.; Wang, D.W. Metabolism Pathways of Arachidonic Acids: Mechanisms and Potential Therapeutic Targets. Signal Transduct. Target. Ther. 2021, 6, 94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bruno, A.; Tacconelli, S.; Contursi, A.; Ballerini, P.; Patrignani, P. Cyclooxygenases and Platelet Functions. Adv. Pharmacol. 2023, 97, 133–165. [Google Scholar] [CrossRef] [Scilit]
- Cho, W.; Choe, J. Prostaglandin E2 Stimulates COX-2 Expression via Mitogen-Activated Protein Kinase P38 but Not ERK in Human Follicular Dendritic Cell-like Cells. BMC Immunol. 2020, 21, 20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ricciotti, E.; Fitzgerald, G.A. Prostaglandins and Inflammation. Arterioscler. Thromb. Vasc. Biol. 2011, 31, 986–1000. [Google Scholar] [CrossRef] [Scilit]
- Okiji, T.; Morita, I.; Sunada, I.; Murota, S. Involvement of Arachidonic Acid Metabolites in Increases in Vascular Permeability in Experimental Dental Pulpal Inflammation in the Rat. Arch. Oral Biol. 1989, 34, 523–528. [Google Scholar] [CrossRef] [Scilit]
- Goodis, H.E.; Bewies, W.R.; Hargreaves, K.M. Prostaglandin E2 Enhances Bradykinin-Evoked ICGRP Release in Bovine Dental Pulp. J. Dent. Res. 2000, 79, 1604–1607. [Google Scholar] [CrossRef] [Scilit]
- Ern, C.; Berger, T.; Frasheri, I.; Heym, R.; Hickel, R.; Folwaczny, M. Differentiation of HMSC and HPDLSC Induced by PGE2 or BMP-7 in 3D Models. Prostaglandins Leukot. Essent. Fat. Acids 2017, 122, 30–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Limjeerajarus, C.N.; Chanarattanubol, T.; Trongkij, P.; Rujiwanichkul, M.; Pavasant, P. Iloprost Induces Tertiary Dentin Formation. J. Endod. 2014, 40, 1784–1790. [Google Scholar] [CrossRef] [Scilit]
- Cohen, J.S.; Reader, A.; Fertel, R.; Michael Beck, F.; Meyers, W.J. A Radioimmunoassay Determination of the Concentrations of Prostaglandins E2 and F2alpha in Painful and Asymptomatic Human Dental Pulps. J. Endod. 1985, 11, 330–335. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakanishi, T.; Matsuo, T.; Ebisu, S. Quantitative Analysis of Immunoglobulins and Inflammatory Factors in Human Pulpal Blood from Exposed Pulps. J. Endod. 1995, 21, 131–136. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petrini, M.; Ferrante, M.; Ciavarelli, L.; Ceccarini, A.; Brunetti, L.; Vacca, M.; Spoto, G. Prostaglandin E2 to Diagnose between Reversible and Irreversible Pulpitis. Int. J. Immunopathol. Pharmacol. 2012, 25, 157–163. [Google Scholar] [CrossRef] [Scilit]
- Okiji, T.; Morita, I.; Kobayashi, C.; Sunada, I.; Murota, S. Arachidonic-Acid Metabolism in Normal and Experimentally-Inflamed Rat Dental Pulp. Arch. Oral Biol. 1987, 32, 723–727. [Google Scholar] [CrossRef] [Scilit]
- Miyauchi, M.; Takata, T.; Ito, H.; Ogawa, I.; Kobayashi, J.; Nikai, H.; Ijuhin, N. Immunohistochemical Demonstration of Prostaglandins E2, F2α, and 6-Keto-Prostaglandin F1α in Rat Dental Pulp with Experimentally Induced Inflammation. J. Endod. 1996, 22, 600–602. [Google Scholar] [CrossRef] [Scilit]
- Chang, M.C.; Chen, Y.J.; Tai, T.F.; Tai, M.R.; Li, M.Y.; Tsai, Y.L.; Lan, W.H.; Wang, Y.L.; Jeng, J.H. Cytokine-Induced Prostaglandin E2 Production and Cyclooxygenase-2 Expression in Dental Pulp Cells: Downstream Calcium Signalling via Activation of Prostaglandin EP Receptor. Int. Endod. J. 2006, 39, 819–826. [Google Scholar] [CrossRef] [Scilit]
- Nakayama, M.; Naito, M.; Omori, K.; Ono, S.; Nakayama, K.; Ohara, N. Porphyromonas Gingivalis Gingipains Induce Cyclooxygenase-2 Expression and Prostaglandin E2 Production via ERK1/2-Activated AP-1 (c-Jun/c-Fos) and IKK/NF-ΚB P65 Cascades. J. Immunol. 2022, 208, 1146–1154. [Google Scholar] [CrossRef] [Scilit]
- Nieboga, E.; Schuster, A.; Drapala, D.M.; Melnykova, M.; Gut, A.; Lipska, W.; Kwitniewski, M.; Migaczewski, M.; Czesnikiewicz-Guzik, M.; Kaczmarzyk, T.; et al. Synergistic Induction of PGE2 by Oral Pathogens and TNF Promotes Gingival Fibroblast-Driven Stromal-Immune Cross-Talk in Periodontitis. MBio 2025, 16, e00046-25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dewhirst, F.E.; Moss, D.E.; Offenbacher, S.; Goodson, J.M. Levels of Prostaglandin E2, Thromboxane, and Prostacyclin in Periodontal Tissues. J. Periodontal Res. 1983, 18, 156–163. [Google Scholar] [CrossRef] [Scilit]
- Tsai, C.C.; Hong, Y.C.; Chen, C.C.; Wu, Y.M. Measurement of Prostaglandin E2 and Leukotriene B4 in the Gingival Crevicular Fluid. J. Dent. 1998, 26, 97–103. [Google Scholar] [CrossRef] [Scilit]
- Ozcelik, F.; Ersahan, S.; Sirin, D.A.; Ozçelik, I.K.; Hepsenoglu, Y.E.; Karip, B. The Importance of Mechanosensitive Cell Mediated Prostaglandin and Nitric Oxide Synthesis in the Pathogenesis of Apical Periodontitis: Comparative with Chronic Periodontitis. Clin. Oral Investig. 2024, 28, 337. [Google Scholar] [CrossRef] [Scilit]
- Salvi, G.E.; Lang, N.P. Host Response Modulation in the Management of Periodontal Diseases. J. Clin. Periodontol. 2005, 32, 108–129. [Google Scholar] [CrossRef] [Scilit]
- Nakashima, K.; Roehrich, N.; Cimasoni, G. Osteocalcin, Prostaglandin E2 and Alkaline Phosphatase in Gingival Crevicular Fluid: Their Relations to Periodontal Status. J. Clin. Periodontol. 1994, 21, 327–333. [Google Scholar] [CrossRef] [Scilit]
- Monzón, J.; Juárez, R.P.A.; Acuña, M.J.; Caramello, C.R. Presencia de Prostaglandina E2 Del Fluido Crevicular En Relación Con El Estado Clínico-Radiográfico Del Periodonto. Acta Odontol. Colomb. 2016, 6, 11–21. [Google Scholar]
- Leibur, E.; Tuhkanen, A.; Pintson, Ü.; Söder, P.Ö. Prostaglandin E2 Levels in Blood Plasma and in Crevicular Fluid of Advanced Periodontitis Patients before and after Surgical Therapy. Oral Dis. 1999, 5, 223–228. [Google Scholar] [CrossRef] [Scilit]
- Takayama, S.I.; Miki, Y.; Shimauchi, H.; Okada, H. Relationship between Prostaglandin E2 Concentrations in Periapical Exudates from Root Canals and Clinical Findings of Periapical Periodontitis. J. Endod. 1996, 22, 677–680. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jang, D.I.; Lee, A.H.; Shin, H.Y.; Song, H.R.; Park, J.H.; Kang, T.B.; Lee, S.R.; Yang, S.H. The Role of Tumor Necrosis Factor Alpha (TNF-α) in Autoimmune Disease and Current TNF-α Inhibitors in Therapeutics. Int. J. Mol. Sci. 2021, 22, 2719. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hassan, A.F.; Kheraldine, H.; Abujamous, L.; Al-Thawadi, H.; Elhissi, A. Inflammation-Associated Drug Resistance and Tumor Growth in TNBC. Front. Immunol. 2025, 16, 1623137. [Google Scholar] [CrossRef] [Scilit]
- Barbero-Navarro, I.; Irigoyen-Camacho, M.E.; Zepeda-Zepeda, M.A.; Ribas-Perez, D.; Castaño-Seiquer, A.; Sofian-Pauliuc, I. Understanding the Dynamics of Inflammatory Cytokines in Endodontic Diagnosis: A Systematic Review. Diagnostics 2024, 14, 1099. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karrabi, M.; Baghani, Z.; Assarzadeh, H. Gingival Crevicular Fluid Level of Tumor Necrosis Factor-Alpha as a Valuable Biomarker for Estimation of the Efficacy of Adjunctive Antimicrobial Photodynamic Therapy in Stage II-IV Periodontitis: A Systematic Review and Meta-Analysis. Lasers Med. Sci. 2024, 39, 301. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakayama, K.; Hirata-Tsuchiya, S.; Okamoto, K.; Morotomi, T.; Jimi, E.; Kitamura, C. The Novel NF-ΚB Inhibitor, MTI-II Peptide Anti-Inflammatory Drug, Suppresses Inflammatory Responses in Odontoblast-Like Cells. J. Cell. Biochem. 2016, 117, 2552–2558. [Google Scholar] [CrossRef] [Scilit]
- Nozu, A.; Hamano, S.; Tomokiyo, A.; Hasegawa, D.; Sugii, H.; Yoshida, S.; Mitarai, H.; Taniguchi, S.; Wada, N.; Maeda, H. Senescence and Odontoblastic Differentiation of Dental Pulp Cells. J. Cell. Physiol. 2018, 234, 849–859. [Google Scholar] [CrossRef] [Scilit]
- Paula-Silva, F.W.G.; Ghosh, A.; Silva, L.A.B.; Kapila, Y.L. TNF-Alpha Promotes an Odontoblastic Phenotype in Dental Pulp Cells. J. Dent. Res. 2009, 88, 339–344. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Keller, J.F.; Carrouel, F.; Staquet, M.J.; Kufer, T.A.; Baudouin, C.; Msika, P.; Bleicher, F.; Farges, J.C. Expression of NOD2 Is Increased in Inflamed Human Dental Pulps and Lipoteichoic Acid-Stimulated Odontoblast-like Cells. Innate Immun. 2011, 17, 29–34. [Google Scholar] [CrossRef] [Scilit]
- Paris, S.; Wolgin, M.; Kielbassa, A.M.; Pries, A.; Zakrzewicz, A. Gene Expression of Human Beta-Defensins in Healthy and Inflamed Human Dental Pulps. J. Endod. 2009, 35, 520–523. [Google Scholar] [CrossRef] [Scilit]
- Kokkas, A.B.; Goulas, A.; Varsamidis, K.; Mirtsou, V.; Tziafas, D. Irreversible but Not Reversible Pulpitis Is Associated with Up-Regulation of Tumour Necrosis Factor-Alpha Gene Expression in Human Pulp. Int. Endod. J. 2007, 40, 198–203. [Google Scholar] [CrossRef] [Scilit]
- Elsalhy, M.; Azizieh, F.; Raghupathy, R. Cytokines as Diagnostic Markers of Pulpal Inflammation. Int. Endod. J. 2013, 46, 573–580. [Google Scholar] [CrossRef] [Scilit]
- Abd-Elmeguid, A.; Abdeldayem, M.; Kline, L.W.; Moqbel, R.; Vliagoftis, H.; Yu, D.C. Osteocalcin Expression in Pulp Inflammation. J. Endod. 2013, 39, 865–872. [Google Scholar] [CrossRef] [Scilit]
- Pezelj-Ribaric, S.; Anic, I.; Brekalo, I.; Miletic, I.; Hasan, M.; Simunovic-Soskic, M. Detection of Tumor Necrosis Factor α in Normal and Inflamed Human Dental Pulps. Arch. Med. Res. 2002, 33, 482–484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Renard, E.; Gaudin, A.; Bienvenu, G.; Amiaud, J.; Farges, J.C.; Cuturi, M.C.; Moreau, A.; Alliot-Licht, B. Immune Cells and Molecular Networks in Experimentally Induced Pulpitis. J. Dent. Res. 2016, 95, 196–205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Y.; Gan, Y.; Lu, J.; Feng, Q.; Wang, H.; Guan, H.; Jiang, Q. Pulpal Tissue Inflammatory Reactions after Experimental Pulpal Exposure in Mice. J. Endod. 2017, 43, 90–95. [Google Scholar] [CrossRef] [Scilit]
- Garlet, G.P.; Cardoso, C.R.B.; Campanelli, A.P.; Ferreira, B.R.; Avila-Campos, M.J.; Cunha, F.Q.; Silva, J.S. The Dual Role of P55 Tumour Necrosis Factor-Alpha Receptor in Actinobacillus Actinomycetemcomitans-Induced Experimental Periodontitis: Host Protection and Tissue Destruction. Clin. Exp. Immunol. 2007, 147, 128–138. [Google Scholar] [CrossRef] [Scilit]
- Graves, D.T.; Delima, A.J.; Assuma, R.; Amar, S.; Oates, T.; Cochran, D. Interleukin-1 and Tumor Necrosis Factor Antagonists Inhibit the Progression of Inflammatory Cell Infiltration toward Alveolar Bone in Experimental Periodontitis. J. Periodontol. 1998, 69, 1419–1425. [Google Scholar] [CrossRef] [Scilit]
- Lima, V.; Vidal, F.D.P.; Rocha, F.A.C.; Brito, G.A.C.; Ribeiro, R.A. Effects of Tumor Necrosis Factor-α Inhibitors Pentoxifylline and Thalidomide on Alveolar Bone Loss in Short-Term Experimental Periodontal Disease in Rats. J. Periodontol. 2004, 75, 162–168. [Google Scholar] [CrossRef] [Scilit]
- Muñoz-Carrillo, J.L.; Hernández-Reyes, V.E.; García-Huerta, O.E.; Chávez-Ruvalcaba, F.; Chávez-Ruvalcaba, M.I.; Chávez-Ruvalcaba, K.M.; Díaz-Alfaro, L. Pathogenesis of Periodontal Disease. In Periodontal Disease—Diagnostic and Adjunctive Non-Surgical Considerations; Nermin Mohammed, A.Y., Ed.; IntechOpen: London, UK, 2019; pp. 1–14. ISBN 978-1-78984-461-0. [Google Scholar]
- Neurath, N.; Kesting, M. Cytokines in Gingivitis and Periodontitis: From Pathogenesis to Therapeutic Targets. Front. Immunol. 2024, 15, 1435054. [Google Scholar] [CrossRef] [Scilit]
- Afacan, B.; Öztürk, V.Ö.; Paşalı, Ç.; Bozkurt, E.; Köse, T.; Emingil, G. Gingival Crevicular Fluid and Salivary HIF-1α, VEGF, and TNF-α Levels in Periodontal Health and Disease. J. Periodontol. 2019, 90, 788–797. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neto, N.D.; Porpino, M.T.M.; Antunes, H.D.S.; Rodrigues, R.C.V.; Perez, A.R.; Pires, F.R.; Siqueira, J.F.; Armada, L. Pro-Inflammatory and Anti-Inflammatory Cytokine Expression in Post-Treatment Apical Periodontitis. J. Appl. Oral Sci. 2018, 26, e20170455. [Google Scholar] [CrossRef] [Scilit]
- Graves, D.T.; Cochran, D. The Contribution of Interleukin-1 and Tumor Necrosis Factor to Periodontal Tissue Destruction. J. Periodontol. 2003, 74, 391–401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kurtiş, B.; Tüter, G.; Serdar, M.; Akdemir, P.; Uygur, C.; Firatli, E.; Bal, B. Gingival Crevicular Fluid Levels of Monocyte Chemoattractant Protein-1 and Tumor Necrosis Factor-Alpha in Patients with Chronic and Aggressive Periodontitis. J. Periodontol. 2005, 76, 1849–1855. [Google Scholar] [CrossRef] [Scilit]
- Delima, A.J.; Oates, T.; Assuma, R.; Schwartz, Z.; Cochran, D.; Amar, S.; Graves, D.T. Soluble Antagonists to Interleukin-1 (IL-1) and Tumor Necrosis Factor (TNF) Inhibits Loss of Tissue Attachment in Experimental PeriodontitisLösliche Antagonisten von Interleukine-1 (IL-1) Und Tumor-Nekrosefaktor (TNF) Hemmen Bei Einer Experimentellen Parodontitis Den AttachmentverlustLes Antagonistes Solubles à l’interleukine-1 et Le Facteur de Nécrose Tumorale Inhibent La Perte d’attache Tissulaire En Présence de Parodontite Expérimentale. J. Clin. Periodontol. 2001, 28, 233–240. [Google Scholar] [CrossRef] [Scilit]
- Martínez-García, M.; Hernández-Lemus, E. Periodontal Inflammation and Systemic Diseases: An Overview. Front. Physiol. 2021, 12, 709438. [Google Scholar] [CrossRef] [Scilit]
- Jain, P.; Ved, A.; Dubey, R.; Singh, N.; Parihar, A.S.; Maytreyee, R. Comparative Evaluation of Serum Tumor Necrosis Factor α in Health and Chronic Periodontitis: A Case–Control Study. Contemp. Clin. Dent. 2020, 11, 342. [Google Scholar] [CrossRef] [Scilit]
- Yucel-Lindberg, T.; Båge, T. Inflammatory Mediators in the Pathogenesis of Periodontitis. Expert Rev. Mol. Med. 2013, 15, e7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kitaura, H.; Marahleh, A.; Ohori, F.; Noguchi, T.; Shen, W.R.; Qi, J.; Nara, Y.; Pramusita, A.; Kinjo, R.; Mizoguchi, I. Osteocyte-Related Cytokines Regulate Osteoclast Formation and Bone Resorption. Int. J. Mol. Sci. 2020, 21, 5169. [Google Scholar] [CrossRef] [Scilit]
- Hienz, S.A.; Paliwal, S.; Ivanovski, S. Mechanisms of Bone Resorption in Periodontitis. J. Immunol. Res. 2015, 2015, 615486. [Google Scholar] [CrossRef] [Scilit]
- Almeida-Junior, L.A.; de Carvalho, M.S.; Almeida, L.K.Y.; Silva-Sousa, A.C.; Sousa-Neto, M.D.; Silva, R.A.B.; Silva, L.A.B.; Paula-Silva, F.W.G. TNF-α–TNFR1 Signaling Mediates Inflammation and Bone Resorption in Apical Periodontitis. J. Endod. 2023, 49, 1319–1328.e2. [Google Scholar] [CrossRef] [Scilit]
- Kitaura, H.; Marahleh, A.; Ohori, F.; Noguchi, T.; Nara, Y.; Pramusita, A.; Kinjo, R.; Ma, J.; Kanou, K.; Mizoguchi, I. Role of the Interaction of Tumor Necrosis Factor-α and Tumor Necrosis Factor Receptors 1 and 2 in Bone-Related Cells. Int. J. Mol. Sci. 2022, 23, 1481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ohori, F.; Kitaura, H.; Ogawa, S.; Shen, W.R.; Qi, J.; Noguchi, T.; Marahleh, A.; Nara, Y.; Pramusita, A.; Mizoguchi, I. IL-33 Inhibits TNF-α-Induced Osteoclastogenesis and Bone Resorption. Int. J. Mol. Sci. 2020, 21, 1130. [Google Scholar] [CrossRef] [Scilit]
- Azuma, Y.; Kaji, K.; Katogi, R.; Takeshita, S.; Kudo, A. Tumor Necrosis Factor-α Induces Differentiation of and Bone Resorption by Osteoclasts. J. Biol. Chem. 2000, 275, 4858–4864. [Google Scholar] [CrossRef] [Scilit]
- Suzuki, Y.; Aoki, K.; Saito, H.; Umeda, M.; Nitta, H.; Baron, R.; Ohya, K.A. Tumor Necrosis Factor-α Antagonist Inhibits Inflammatory Bone Resorption Induced by Porphyromonas Gingivalis Infection in Mice. J. Periodontal Res. 2006, 41, 81–91. [Google Scholar] [CrossRef] [Scilit]
- Gümüş, P.; Nizam, N.; Nalbantsoy, A.; Özçaka, Ö.; Buduneli, N.S. Serum Levels of Interleukin-21, -33 and Prostaglandin E2 in Patients with Generalised Aggressive or Chronic Periodontitis. Oral Health Prev. Dent. 2017, 15, 385–390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perunovic, N.D.; Rakic, M.M.; Nikolic, L.I.; Jankovic, S.M.; Aleksic, Z.M.; Plecas, D.V.; Madianos, P.N.; Cakic, S.S. The Association Between Periodontal Inflammation and Labor Triggers (Elevated Cytokine Levels) in Preterm Birth: A Cross-Sectional Study. J. Periodontol. 2016, 87, 248–256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, R.P.H.; Huang, J.; Chan, K.W.Y.; Leung, W.K.; Goto, T.; Ho, Y.S.; Chang, R.C.C. IL-1β and TNF-α Play an Important Role in Modulating the Risk of Periodontitis and Alzheimer’s Disease. J. Neuroinflamm. 2023, 20, 71. [Google Scholar] [CrossRef] [Scilit]
- Andrukhov, O.; Ulm, C.; Reischl, H.; Nguyen, P.Q.; Matejka, M.; Rausch-Fan, X. Serum Cytokine Levels in Periodontitis Patients in Relation to the Bacterial Load. J. Periodontol. 2011, 82, 885–892. [Google Scholar] [CrossRef] [Scilit]
- Nilsson, M.; Kopp, S. Gingivitis and Periodontitis Are Related to Repeated High Levels of Circulating Tumor Necrosis Factor-Alpha in Patients with Rheumatoid Arthritis. J. Periodontol. 2008, 79, 1689–1696. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bletsa, A.; Berggreen, E.; Fristad, I.; Tenstad, O.; Wiig, H. Cytokine Signalling in Rat Pulp Interstitial Fluid and Transcapillary Fluid Exchange during Lipopolysaccharide-Induced Acute Inflammation. J. Physiol. 2006, 573, 225–236. [Google Scholar] [CrossRef] [Scilit]
- Arfeen, M.; Srivastava, A.; Srivastava, N.; Khan, R.A.; Almahmoud, S.A.; Mohammed, H.A. Design, Classification, and Adverse Effects of NSAIDs: A Review on Recent Advancements. Bioorg. Med. Chem. 2024, 112, 117899. [Google Scholar] [CrossRef] [Scilit]
- Bindu, S.; Mazumder, S.; Bandyopadhyay, U. Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) and Organ Damage: A Current Perspective. Biochem. Pharmacol. 2020, 180, 114147. [Google Scholar] [CrossRef] [Scilit]
- Ha, M.W.; Paek, S.M. Recent Advances in the Synthesis of Ibuprofen and Naproxen. Molecules 2021, 26, 4792. [Google Scholar] [CrossRef] [Scilit]
- Rainsford, K.D. Ibuprofen: Pharmacology, Efficacy and Safety. Inflammopharmacology 2009, 17, 275–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jan-Roblero, J.; Cruz-Maya, J.A. Ibuprofen: Toxicology and Biodegradation of an Emerging Contaminant. Molecules 2023, 28, 2097. [Google Scholar] [CrossRef] [Scilit]
- Mazaleuskaya, L.L.; Theken, K.N.; Gong, L.; Thorn, C.F.; Fitzgerald, G.A.; Altman, R.B.; Klein, T.E. PharmGKB Summary: Ibuprofen Pathways. Pharmacogenet. Genom. 2015, 25, 96–106. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, V.; Chen, Y.W.; Johnson, J.D.; Paranjpe, A. In Vivo Evaluation of Effect of Preoperative Ibuprofen on Proinflammatory Mediators in Irreversible Pulpitis Cases. J. Endod. 2020, 46, 1210–1216. [Google Scholar] [CrossRef] [Scilit]
- Su, J.; Gu, J.; Dong, Z.; Mei, B. Ibuprofen Rescues Abnormalities in Periodontal Tissues in Conditional Presenilin 1 and Presenilin 2 Double Knockout Mice. Int. J. Mol. Sci. 2013, 14, 18457–18469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shahriari, S.; Rezaei, A.; Mohsen Jalalzadeh, S.; Mani, K.; Zamani, A. Effect of Ibuprofen on IL-1β, TNF-α and PGE2 Levels in Periapical Exudates: A Double Blinded Clinical Trial. Iran. J. Immunol. 2011, 8, 176–182. [Google Scholar] [CrossRef]
- Lessard, G.M.; Torabinejad, M.; Swope, D. Arachidonic Acid Metabolism in Canine Tooth Pulps and the Effects of Nonsteroidal Anti-Inflammatory Drugs. J. Endod. 1986, 12, 146–149. [Google Scholar] [CrossRef] [Scilit]
- Hutchins, M.; Housholder, G.; Suchina, J.; Rittman, B.; Rittman, G.; Montgomery, E. Comparison of Acetaminophen, Ibuprofen, and Nabumetone Therapy in Rats with Pulpal Pathosis. J. Endod. 1999, 25, 804–806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elattar, T.M.A.; Lin, H.S.; Tira, D.E. The Effect of Non-Steroidal Anti-Inflammatory Drugs on the Metabolism of 14C-Arachidonic Acid by Human Gingival Tissue in Vitro. J. Dent. Res. 1983, 62, 975–979. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Offenbacher, S.; Odle, B.M.; Green, M.D.; Mayambala, C.S.; Smith, M.A.; Fritz, M.E.; van Dyke, T.E.; Yeh, K.C.; Sena, F.J. Inhibition of Human Periodontal Prostaglandin E2 Synthesis with Selected Agents. Agents Actions 1990, 29, 232–238. [Google Scholar] [CrossRef] [Scilit]
- O’Brien, T.P.; Roszkowski, M.T.; Wolff, L.F.; Hinrichs, J.E.; Hargreaves, K.M. Effect of a Non-Steroidal Anti-Inflammatory Drug on Tissue Levels of Immunoreactive Prostaglandin E2, Immunoreactive Leukotriene, and Pain after Periodontal Surgery. J. Periodontol. 1996, 67, 1307–1316. [Google Scholar] [CrossRef] [Scilit]
- Offenbacher, S.; Williams, R.C.; Jeffcoat, M.K.; Howell, T.H.; Odle, B.M.; Smith, M.A.; Hall, C.M.; Johnson, H.G.; Goldhaber, P. Effects of NSAIDs on Beagle Crevicular Cyclooxygenase Metabolites and Periodontal Bone Loss. J. Periodontal Res. 1992, 27, 207–213. [Google Scholar] [CrossRef] [Scilit]
- Gomes, B.P.F.A.; Berber, V.B.; Marinho, A.C.S.; Louzada, L.M.; Arruda-Vasconcelos, R.; Passini, M.R.Z.; Lopes, E.M.; Pecorari, V.G.A.; Chen, T.; Paster, B.J. Chemomechanical Preparation Influences the Microbial Community and the Levels of LPS, LTA and Cytokines in Combined Endodontic-Periodontal Lesions: A Clinical Study. J. Periodontal Res. 2022, 57, 341–356. [Google Scholar] [CrossRef] [Scilit]
- Sun, X.N.; Song, A.M.; Yang, P.S. Short-Term Effect of Ibuprofen on Clinical Indexes and Cytokines in the Gingival Crevicular Fluid of Patients with Severe Chronic Periodontitis. Shanghai Kou Qiang Yi Xue 2017, 26, 557–560. [Google Scholar]
- Batool, F.; Agossa, K.; Lizambard, M.; Petit, C.; Bugueno, I.M.; Delcourt-Debruyne, E.; Benkirane-Jessel, N.; Tenenbaum, H.; Siepmann, J.; Siepmann, F.; et al. In-Situ Forming Implants Loaded with Chlorhexidine and Ibuprofen for Periodontal Treatment: Proof of Concept Study in Vivo. Int. J. Pharm. 2019, 569, 118564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, Q.; Jin, Y.; Chen, X.; Ye, X.; Shen, X.; Lin, M.; Zeng, C.; Zhou, T.; Zhang, J. NF-ΚB in Biology and Targeted Therapy: New Insights and Translational Implications. Signal Transduct. Target. Ther. 2024, 9, 53. [Google Scholar] [CrossRef] [Scilit]
- Cazanave, S.; Vadrot, N.; Tinel, M.; Berson, A.; Lettéron, P.; Larosche, I.; Descatoire, V.; Feldmann, G.; Robin, M.A.; Pessayre, D. Ibuprofen Administration Attenuates Serum TNF-α Levels, Hepatic Glutathione Depletion, Hepatic Apoptosis and Mouse Mortality after Fas Stimulation. Toxicol. Appl. Pharmacol. 2008, 231, 336–343. [Google Scholar] [CrossRef] [Scilit]
- Takada, Y.; Bhardwaj, A.; Potdar, P.; Aggarwal, B.B. Nonsteroidal Anti-Inflammatory Agents Differ in Their Ability to Suppress NF-KappaB Activation, Inhibition of Expression of Cyclooxygenase-2 and Cyclin D1, and Abrogation of Tumor Cell Proliferation. Oncogene 2004, 23, 9247–9258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dauletbaev, N.; Lam, J.; Eklove, D.; Iskandar, M.; Lands, L.C. Ibuprofen Modulates NF-ĸB Activity but Not IL-8 Production in Cystic Fibrosis Respiratory Epithelial Cells. Respiration 2010, 79, 234–242. [Google Scholar] [CrossRef] [Scilit]
- Heasman, P.A.; Hughes, F.J. Drugs, Medications and Periodontal Disease. Br. Dent. J. 2014, 217, 411–419. [Google Scholar] [CrossRef] [Scilit]
- Ronchetti, S.; Migliorati, G.; Bruscoli, S.; Riccardi, C. Defining the Role of Glucocorticoids in Inflammation. Clin. Sci. 2018, 132, 1529–1543. [Google Scholar] [CrossRef] [Scilit]
- Cain, D.W.; Cidlowski, J.A. Immune Regulation by Glucocorticoids. Nat. Rev. Immunol. 2017, 17, 233–247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shimba, A.; Ikuta, K. Control of Immunity by Glucocorticoids in Health and Disease. Semin. Immunopathol. 2020, 42, 669–680. [Google Scholar] [CrossRef] [Scilit]
- Harvey, B.J. Molecular Mechanisms of Dexamethasone Actions in COVID-19: Ion Channels and Airway Surface Liquid Dynamics. Steroids 2024, 202, 109348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dildar, I.; Moghal, A.; Mirza, A.; Zaheer, M.A.; Mallick, M.R.; Munir, S. Evaluation of Postoperative Pain after Using Dexamethasone Intracanal Rinse in Irreversible Pulpitis. J. Coll. Physicians Surg. Pak. 2024, 34, 390–393. [Google Scholar] [CrossRef] [Scilit]
- Sekhar, R.M.; Nirmala, S.; Chukka, R.R.; Goud, S.; Kumar, N.; Patil, D. Comparing the Effects of Intramuscular Injections of Dexamethasone and Ketorolac Tromethamine on Post-Treatment Endodontic Pain: An In Vivo Study. Cureus 2024, 16, e57086. [Google Scholar] [CrossRef] [Scilit]
- Franco-de la Torre, L.; Gómez-Sánchez, E.; Serafín-Higuera, N.A.; Alonso-Castro, Á.J.; López-Verdín, S.; Molina-Frechero, N.; Granados-Soto, V.; Isiordia-Espinoza, M.A. Dexamethasone Increases the Anesthetic Success in Patients with Symptomatic Irreversible Pulpitis: A Meta-Analysis. Pharmaceuticals 2022, 15, 878. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rodrigues, G.A.; Hizatugu, R.; Bronzato, J.D.; de-Jesus-Soares, A.; Frozoni, M. Effect of Preemptive Use of a Nonsteroidal Anti-Inflammatory Drug and a Corticosteroid on the Efficacy of Inferior Alveolar Nerve Blockade and Postoperative Pain Control in Endodontic Treatment of Molars with Symptomatic Pulpitis: A Randomized Double-Blind Placebo-Controlled Clinical Trial. Int. Endod. J. 2024, 57, 520–532. [Google Scholar] [CrossRef] [Scilit]
- Hegde, V.; Shanmugasundaram, S.; Shaikh, S.; Kulkarni, V.; Suresh, N.; Setzer, F.C.; Nagendrababu, V. Effect of Preoperative Oral Steroids in Comparison to Anti-Inflammatory on Anesthetic Success of Inferior Alveolar Nerve Block in Mandibular Molars with Symptomatic Irreversible Pulpitis—A Double-Blinded Randomized Clinical Trial. J. Endod. 2023, 49, 354–361. [Google Scholar] [CrossRef] [Scilit]
- Elnaghy, A.M.; Elshazli, A.H.; Elsaka, S.E. Effectiveness of Oral Premedication of Meloxicam, Ketorolac, Dexamethasone, and Ibuprofen on the Success Rate of Inferior Alveolar Nerve Block in Patients with Symptomatic Irreversible Pulpitis: A Prospective, Double-Blind, Randomized Controlled Trial. Quintessence Int. 2023, 54, 92–99. [Google Scholar] [CrossRef] [Scilit]
- Liu, X.; Xie, Y.; Gao, W.; Zhan, L.; Hu, L.; Zuo, L.; Li, Y. Experimental Study of Dexamethasone-Loaded Hollow Hydroxyapatite Microspheres Applied to Direct Pulp Capping of Rat Molars. Front. Endocrinol. 2023, 14, 1192420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Steffens, J.P.; Santos, F.A.; Pilatti, G.L. Postoperative Periodontal Pain Prevention Using Two Dexamethasone Medication Protocols: A Double-Blind, Parallel-Group, Placebo-Controlled Randomized Clinical Trial. Am. J. Dent. 2011, 24, 354–356. [Google Scholar] [PubMed]
- Saglie, F.R.; Simon, K.; Merrill, J.; Koeffler, H.P. Lipopolysaccharide from Actinobacillus Actinomycetemcomitans Stimulates Macrophages to Produce Interleukin-1 and Tumor Necrosis Factor MRNA and Protein. Oral Microbiol. Immunol. 1990, 5, 256–262. [Google Scholar] [CrossRef] [Scilit]
- Reddi, K.; Nair, S.P.; White, P.A.; Hodges, S.; Tabona, P.; Meghji, S.; Poole, S.; Wilson, M.; Henderson, B. Surface-Associated Material from the Bacterium Actinobacillus Actinomycetemcomitans Contains a Peptide Which, in Contrast to Lipopolysaccharide, Directly Stimulates Fibroblast Interleukin-6 Gene Transcription. Eur. J. Biochem. 1996, 236, 871–876. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Modéer, T.; Andurén, I.; Yucel-Lindberg, T. Bradykinin Synergistically Stimulates Interleukin 6 Production in Human Gingival Fibroblasts Challenged with Interleukin 1 or Tumour Necrosis Factor α. Cytokine 1998, 10, 26–31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sakaki, H.; Matsumiya, T.; Kusumi, A.; Imaizumi, T.; Satoh, H.; Yoshida, H.; Satoh, K.; Kimura, H. Interleukin-1beta Induces Matrix Metalloproteinase-1 Expression in Cultured Human Gingival Fibroblasts: Role of Cyclooxygenase-2 and Prostaglandin E2. Oral Dis. 2004, 10, 87–93. [Google Scholar] [CrossRef] [Scilit]
- Ono, M.; Kantoh, K.; Ueki, J.; Shimada, A.; Wakabayashi, H.; Matsuta, T.; Sakagami, H.; Kumada, H.; Hamada, N.; Kitajima, M.; et al. Quest for Anti-Inflammatory Substances Using IL-1β-Stimulated Gingival Fibroblasts. Vivo 2011, 25, 763–768. [Google Scholar]
- Li, N.; Xie, L.; Wu, Y.; Wu, Y.; Liu, Y.; Gao, Y.; Yang, J.; Zhang, X.; Jiang, L. Dexamethasone-Loaded Zeolitic Imidazolate Frameworks Nanocomposite Hydrogel with Antibacterial and Anti-Inflammatory Effects for Periodontitis Treatment. Mater. Today Bio 2022, 16, 100360. [Google Scholar] [CrossRef] [Scilit]
- Yucel-Lindberg, T.; Hallström, T.; Kats, A.; Mustafa, M.; Modéer, T. Induction of Microsomal Prostaglandin E Synthase-1 in Human Gingival Fibroblasts. Inflammation 2004, 28, 89–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Båge, T.; Modéer, T.; Kawakami, T.; Quezada, H.C.; Yucel-Lindberg, T. Regulation of Prostaglandin E Synthases: Effects of SiRNA-Mediated Inhibition of Microsomal Prostaglandin E Synthase-1. Biochim. Biophys. Acta 2007, 1773, 1589–1598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yucel-Lindberg, T.; Ahola, H.; Nilsson, S.; Carlstedt-Duke, J.; Modéer, T. Interleukin-1 Beta Induces Expression of Cyclooxygenase-2 MRNA in Human Gingival Fibroblasts. Inflammation 1995, 19, 549–560. [Google Scholar] [CrossRef] [Scilit]
- Nakao, S.; Ogata, Y.; Modéer, T.; Segawa, M.; Furuyama, S.; Sugiya, H. Bradykinin Induces a Rapid Cyclooxygenase-2 MRNA Expression via Ca2+ Mobilization in Human Gingival Fibroblasts Primed with Interleukin-1 Beta. Cell Calcium 2001, 29, 446–452. [Google Scholar] [CrossRef] [Scilit]
- Yucel-Lindberg, T.; Nilsson, S.; Modéer, T. Signal Transduction Pathways Involved in the Synergistic Stimulation of Prostaglandin Production by Interleukin-1beta and Tumor Necrosis Factor Alpha in Human Gingival Fibroblasts. J. Dent. Res. 1999, 78, 61–68. [Google Scholar] [CrossRef] [Scilit]
- Nakao, S.; Ogata, Y.; Modéer, T.; Furuyama, S.; Sugiya, H. Bradykinin Potentiates Prostaglandin E2 Release in the Human Gingival Fibroblasts Pretreated with Interleukin-1β via Ca2+ Mobilization. Eur. J. Pharmacol. 2000, 395, 247–253. [Google Scholar] [CrossRef] [Scilit]
- Noguchi, K.; Shitashige, M.; Yanai, M.; Morita, I.; Nishihara, T.; Murota, S.; Ishikawa, I. Prostaglandin Production via Induction of Cyclooxygenase-2 by Human Gingival Fibroblasts Stimulated with Lipopolysaccharides. Inflammation 1996, 20, 555–568. [Google Scholar] [CrossRef] [Scilit]
- Domeij, H.; Yucel-Lindberg, T.; Modéer, T. Signal Pathways Involved in the Production of MMP-1 and MMP-3 in Human Gingival Fibroblasts. Eur. J. Oral Sci. 2002, 110, 302–306. [Google Scholar] [CrossRef] [Scilit]
- Okada, N.; Kobayashi, M.; Mugikura, K.; Okamatsu, Y.; Hanazawa, S.; Kitano, S.; Hasegawa, K. Interleukin-6 Production in Human Fibroblasts Derived from Periodontal Tissues Is Differentially Regulated by Cytokines and a Glucocorticoid. J. Periodontal Res. 1997, 32, 559–569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Noguchi, K.; Shitashige, M.; Ishikawa, I. Involvement of Cyclooxygenase-2 in Interleukin-1alpha-Induced Prostaglandin Production by Human Periodontal Ligament Cells. J. Periodontol. 1999, 70, 902–908. [Google Scholar] [CrossRef] [Scilit]
- Holanda Pinto, S.A.; Pinto, L.M.S.; Cunha, G.M.A.; Chaves, M.H.; Santos, F.A.; Rao, V.S. Anti-Inflammatory Effect of Alpha, Beta-Amyrin, a Pentacyclic Triterpene from Protium Heptaphyllum in Rat Model of Acute Periodontitis. Inflammopharmacology 2008, 16, 48–52. [Google Scholar] [CrossRef] [Scilit]
- Cavagni, J.; Soletti, A.C.; Gaio, E.J.; Rösing, C.K. The Effect of Dexamethasone in the Pathogenesis of Ligature-Induced Periodontal Disease in Wistar Rats. Braz. Oral Res. 2005, 19, 290–294. [Google Scholar] [CrossRef] [Scilit]
- Breivik, T.; Gundersen, Y.; Osmundsen, H.; Fonnum, F.; Opstad, P.K. Neonatal Dexamethasone and Chronic Tianeptine Treatment Inhibit Ligature-Induced Periodontitis in Adult Rats. J. Periodontal Res. 2006, 41, 23–32. [Google Scholar] [CrossRef] [Scilit]
- de Almeida, J.M.; Matheus, H.R.; Fiorin, L.G.; Furquim, E.M.A.; Gusman, D.J.R. Influence of Immunosuppression on the Progression of Experimental Periodontitis and on Healthy Periodontal Tissue: A Rat in Vivo Study. J. Dent. Res. Dent. Clin. Dent. Prospects 2021, 15, 94–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sousa, L.H.T.; Moura, E.V.; Queiroz, A.L.; Val, D.; Chaves, H.; Lisboa, M.; Furlaneto, F.; Brito, G.A.; Goes, P. Effects of Glucocorticoid-Induced Osteoporosis on Bone Tissue of Rats with Experimental Periodontitis. Arch. Oral Biol. 2017, 77, 55–61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferrari, A.M.; Byers, M.R. Chronic Dexamethasone Treatment and Its Effects on Sensory Neuropeptides, Pulpal Injury Reactions and Reparative Dentin. Brain Res. 1996, 723, 125–134. [Google Scholar] [CrossRef] [Scilit]
- Byers, M.R.; Rafie, M.M.; Westenbroek, R.E. Dexamethasone Effects on Nav1.6 in Tooth Pulp, Dental Nerves, and Alveolar Osteoclasts of Adult Rats. Cell Tissue Res. 2009, 338, 217–226. [Google Scholar] [CrossRef] [Scilit]
- Savitri, I.J.; Komang Evan Wijaksana, I.; Arief, O.; Falah, M.N.; Tedjosasongko, U.; Siswanto, O.B.; Ouhara, K.; Kurihara, H.; Mizuno, N. Aesthetic Consideration in Patient Management of Severe Periodontitis Aggravated by Oral Dexamethasone. Dent. J. (Maj. Kedokt. Gigi) 2023, 56, 73–79. [Google Scholar] [CrossRef] [Scilit]
- He, Y.; Zhang, L.; Zhu, Z.; Xiao, A.; Yu, H.; Gan, X. Blockade of Cyclophilin D Rescues Dexamethasone-Induced Oxidative Stress in Gingival Tissue. PLoS ONE 2017, 12, e017, Erratum in: PLoS ONE 2017, 12, e0175616. https://doi.org/10.1371/journal.pone.0175616. PMID: 28273124; PMCID: PMC5342226.. [Google Scholar] [CrossRef] [Scilit]
- Chen, F.; Hao, L.; Zhu, S.; Yang, X.; Shi, W.; Zheng, K.; Wang, T.; Chen, H. Potential Adverse Effects of Dexamethasone Therapy on COVID-19 Patients: Review and Recommendations. Infect. Dis. Ther. 2021, 10, 1907–1931. [Google Scholar] [CrossRef] [Scilit]
- Polderman, J.A.W.; Farhang-Razi, V.; van Dieren, S.; Kranke, P.; DeVries, J.H.; Hollmann, M.W.; Preckel, B.; Hermanides, J. Adverse Side-Effects of Dexamethasone in Surgical Patients—An Abridged Cochrane Systematic Review. Anaesthesia 2019, 74, 929–939. [Google Scholar] [CrossRef] [Scilit]
- Polderman, J.A.W.; Farhang-Razi, V.; Van Dieren, S.; Kranke, P.; Devries, J.H.; Hollmann, M.W.; Preckel, B.; Hermanides, J. Adverse Side Effects of Dexamethasone in Surgical Patients. Cochrane Database Syst. Rev. 2018, 8, CD011940. [Google Scholar] [CrossRef] [Scilit]
- Chaudhary, P.D.; Rastogi, S.; Gupta, P.; Niranjanaprasad Indra, B.; Thomas, R.; Choudhury, R. Pre-Emptive Effect of Dexamethasone Injection and Consumption on Post-Operative Swelling, Pain, and Trismus after Third Molar Surgery. A Prospective, Double Blind and Randomized Study. J. Oral Biol. Craniofacial Res. 2015, 5, 21–27. [Google Scholar] [CrossRef] [Scilit]
- Waldron, N.H.; Jones, C.A.; Gan, T.J.; Allen, T.K.; Habib, A.S. Impact of Perioperative Dexamethasone on Postoperative Analgesia and Side-Effects: Systematic Review and Meta-Analysis. Br. J. Anaesth. 2013, 110, 191–200. [Google Scholar] [CrossRef] [Scilit]
- Ghazi, S.; Rasul, K.Y.; Hamad, A.K.; Khidhir, A.A.; Ahmed, L.K. Side Effects of Steroidal And Non-Steroidal Anti-Inflammatory Drugs on The Oral Cavity. Erbil Dent. J. 2024, 6, 266–276. [Google Scholar] [CrossRef] [Scilit]
- Jiang, Z.P.; Li, A.G.; Luo, W.; Luo, X.K.; Liang, D.C.; Li, J.; Tang, K.H.; Liu, L.; Long, Z.M.; Miao, R.; et al. Targeting TRPV1 Channels in Desensitized Neural Afferent Pathways May Help Mitigate Pain and Lower Urinary Tract Symptoms Caused by Prostatitis. Front. Pharmacol. 2025, 16, 1541684. [Google Scholar] [CrossRef] [Scilit]
- Singh, S.; Natarajan, K.; Aggarwal, B.B. Capsaicin (8-Methyl-N-Vanillyl-6-Nonenamide) Is a Potent Inhibitor of Nuclear Transcription Factor-Kappa B Activation by Diverse Agents. J. Immunol. 1996, 157, 4412–4420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, C.-W.; Lee, S.T.; Wu, W.T.; Fu, W.M.; Ho, F.M.; Lin, W.W. Signal Transduction for Inhibition of Inducible Nitric Oxide Synthase and Cyclooxygenase-2 Induction by Capsaicin and Related Analogs in Macrophages. Br. J. Pharmacol. 2003, 140, 1077–1087. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ueda, K.; Tsuji, F.; Hirata, T.; Takaoka, M.; Matsumura, Y. Preventive Effect of TRPV1 Agonists Capsaicin and Resiniferatoxin on Ischemia/Reperfusion-Induced Renal Injury in Rats. J. Cardiovasc. Pharmacol. 2008, 51, 513–520. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muñoz-Carrillo, J.L.; Gutiérrez-Coronado, O.; Muñoz-Escobedo, J.J.; Contreras-Cordero, J.F.; Maldonado-Tapia, C.; Moreno-García, M.A. Resiniferatoxin Promotes Adult Worm Expulsion in Trichinella Spiralis-Infected Rats by Th2 Immune Response Modulation. Parasite Immunol. 2021, 43, e12840. [Google Scholar] [CrossRef] [Scilit]
- Muñoz-Carrillo, J.L.; Muñoz-Escobedo, J.J.; Maldonado-Tapia, C.H.; Chávez-Ruvalcaba, F.; Moreno-García, M.A. Resiniferatoxin Lowers TNF-α, NO and PGE2 in the Intestinal Phase and the Parasite Burden in the Muscular Phase of Trichinella Spiralis Infection. Parasite Immunol. 2017, 39, e12393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muñoz-Carrillo, J.L.; Contreras-Cordero, J.F.; Muñoz-López, J.L.; Maldonado-Tapia, C.H.; Muñoz-Escobedo, J.J.; Moreno-García, M.A. Resiniferatoxin Modulates the Th1 Immune Response and Protects the Host during Intestinal Nematode Infection. Parasite Immunol. 2017, 39, e12448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balaha, D.A.A.; Ismail, H.I.H.; Risk, O.M.K.; Gamea, G.A.M. Effect of Resiniferatoxin as an Anti-Inflammatory Drug on Experimental Trichinellosis. Int. J. Curr. Microbiol. Appl. Sci 2020, 9, 2906–2922. [Google Scholar] [CrossRef] [Scilit]
- Hajishengallis, G.; Korostoff, J.M. Revisiting the Page & Schroeder Model: The Good, the Bad and the Unknowns in the Periodontal Host Response 40 Years Later. Periodontology 2000 2017, 75, 116–151. [Google Scholar] [CrossRef] [Scilit]
- Gemmell, E.; Yamazaki, K.; Seymour, G.J. The Role of T Cells in Periodontal Disease: Homeostasis and Autoimmunity. Periodontology 2000 2007, 43, 14–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Farges, J.C.; Alliot-Licht, B.; Renard, E.; Ducret, M.; Gaudin, A.; Smith, A.J.; Cooper, P.R. Dental Pulp Defence and Repair Mechanisms in Dental Caries. Mediat. Inflamm. 2015, 2015, 230251. [Google Scholar] [CrossRef] [Scilit]
- Kostenkova, A.; Zasčiurinskienė, E.; Lodienė, G. Histopathological Evaluation of the Impact of Periodontitis on Dental Pulp Condition: A Systematic Literature Review. Aust. Endod. J. 2025, 51, 806–824. [Google Scholar] [CrossRef] [Scilit]
- Ilmarinen, P.; Kankaanranta, H. Eosinophil Apoptosis as a Therapeutic Target in Allergic Asthma. Basic Clin. Pharmacol. Toxicol. 2014, 114, 109–117. [Google Scholar] [CrossRef] [Scilit]
- Lamas, A.M.; Leon, O.G.; Schleimer, R.P. Glucocorticoids Inhibit Eosinophil Responses to Granulocyte-Macrophage Colony-Stimulating Factor. J. Immunol. 1991, 147, 254–259. [Google Scholar] [CrossRef] [Scilit]
- Arai, Y.; Nakamura, Y.; Inoue, F.; Yamamoto, K.; Saito, K.; Furusawa, S. Glucocorticoid-Induced Apoptotic Pathways in Eosinophils: Comparison with Glucocorticoid-Sensitive Leukemia Cells. Int. J. Hematol. 2000, 71, 340–349. [Google Scholar]
- Mandell, G.L.; Rubin, W.; Hook, E.W. The Effect of an NADH Oxidase Inhibitor (Hydrocortisone) on Polymorphonuclear Leukocyte Bactericidal Activity. J. Clin. Investig. 1970, 49, 1381–1388. [Google Scholar] [CrossRef] [Scilit]
- Gillis, S.; Crabtree, G.R.; Smith, K.A. Glucocorticoid-Induced Inhibition of T Cell Growth Factor Production: I. The Effect on Mitogen-Induced Lymphocyte Proliferation. J. Immunol. 1979, 123, 1624–1631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uings, I.; Puxeddu, I.; Temkin, V.; Smith, S.J.; Fattah, D.; Ray, K.P.; Levi-Schaffer, F. Effects of Dexamethasone on TNF-Alpha-Induced Release of Cytokines from Purified Human Blood Eosinophils. Clin. Mol. Allergy 2005, 3, 5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levi-Schaffer, F.; Temkin, V.; Malamud, V.; Feld, S.; Zilberman, Y. Mast Cells Enhance Eosinophil Survival in Vitro: Role of TNF-Alpha and Granulocyte-Macrophage Colony-Stimulating Factor. J. Immunol. 1998, 160, 5554–5562. [Google Scholar] [CrossRef] [Scilit]
- Iadarola, M.J.; Sapio, M.R.; Nahama, A.; Mannes, A.J. Intraarticular Resiniferatoxin, a Potent TRPV1 Agonist, for Treatment of Osteoarthritic Pain. Pain Manag. 2025, 15, 659–670. [Google Scholar] [CrossRef] [Scilit]
- Laverdet, B.; Girard, D.; Bayout, A.; Bordeau, N.; Demiot, C.; Desmoulière, A. Effects of Small-Fiber Neuropathy Induced by Resiniferatoxin on Skin Healing and Axonal Regrowth after Burn. Burns 2017, 43, 562–572. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lepiarczyk, E.; Paukszto, Ł.; Wiszpolska, M.; Łopieńska-Biernat, E.; Bossowska, A.; Majewski, M.K.; Majewska, M. Molecular Influence of Resiniferatoxin on the Urinary Bladder Wall Based on Differential Gene Expression Profiling. Cells 2023, 12, 462. [Google Scholar] [CrossRef] [Scilit]
- Brown, D.C.; Agnello, K.; Iadarola, M.J. Intrathecal Resiniferatoxin in a Dog Model: Efficacy in Bone Cancer Pain. Pain 2015, 156, 1018–1024. [Google Scholar] [CrossRef] [Scilit]
- Pan, H.L.; Khan, G.M.; Alloway, K.D.; Chen, S.R. Resiniferatoxin Induces Paradoxical Changes in Thermal and Mechanical Sensitivities in Rats: Mechanism of Action. J. Neurosci. 2003, 23, 2911–2919. [Google Scholar] [CrossRef] [Scilit]
- Zhang, G.F.; Chen, S.R.; Jin, D.; Huang, Y.; Chen, H.; Pan, H.L. A2δ-1 Upregulation in Primary Sensory Neurons Promotes NMDA Receptor-Mediated Glutamatergic Input in Resiniferatoxin-Induced Neuropathy. J. Neurosci. 2021, 41, 5963–5978. [Google Scholar] [CrossRef] [Scilit]
- Lepiarczyk, E.; Maździarz, M.; Paukszto, Ł.; Bossowska, A.; Majewski, M.; Kaleczyc, J.; Łopieńska-Biernat, E.; Jaśkiewicz, Ł.; Skowrońska, A.; Skowroński, M.T.; et al. Transcriptomic Characterization of the Porcine Urinary Bladder Trigone Following Intravesical Administration of Resiniferatoxin: Insights from High-Throughput Sequencing. Toxins 2025, 17, 127. [Google Scholar] [CrossRef] [Scilit]
- de Almeida, A.S.; de Bernardes, L.B.; Trevisan, G. TRP Channels in Cancer Pain. Eur. J. Pharmacol. 2021, 904, 174185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hammad, D.; Ourhzif, E.M.; Hamri, S.; Abderrafia, H.; Khouili, M.; Pujol, M.D. Chemical Components of the Dried Latex of Euphorbia Resinifera Berg and Its Medicinal Features. Chem. Biodivers. 2025, 22, e202403067. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Connor, J.; Makonnen, E.; Rostom, A. Comparison of Analgesic Effects of Khat (Catha Edulis Forsk) Extract, D-Amphetamine and Ibuprofen in Mice. J. Pharm. Pharmacol. 2000, 52, 107–110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
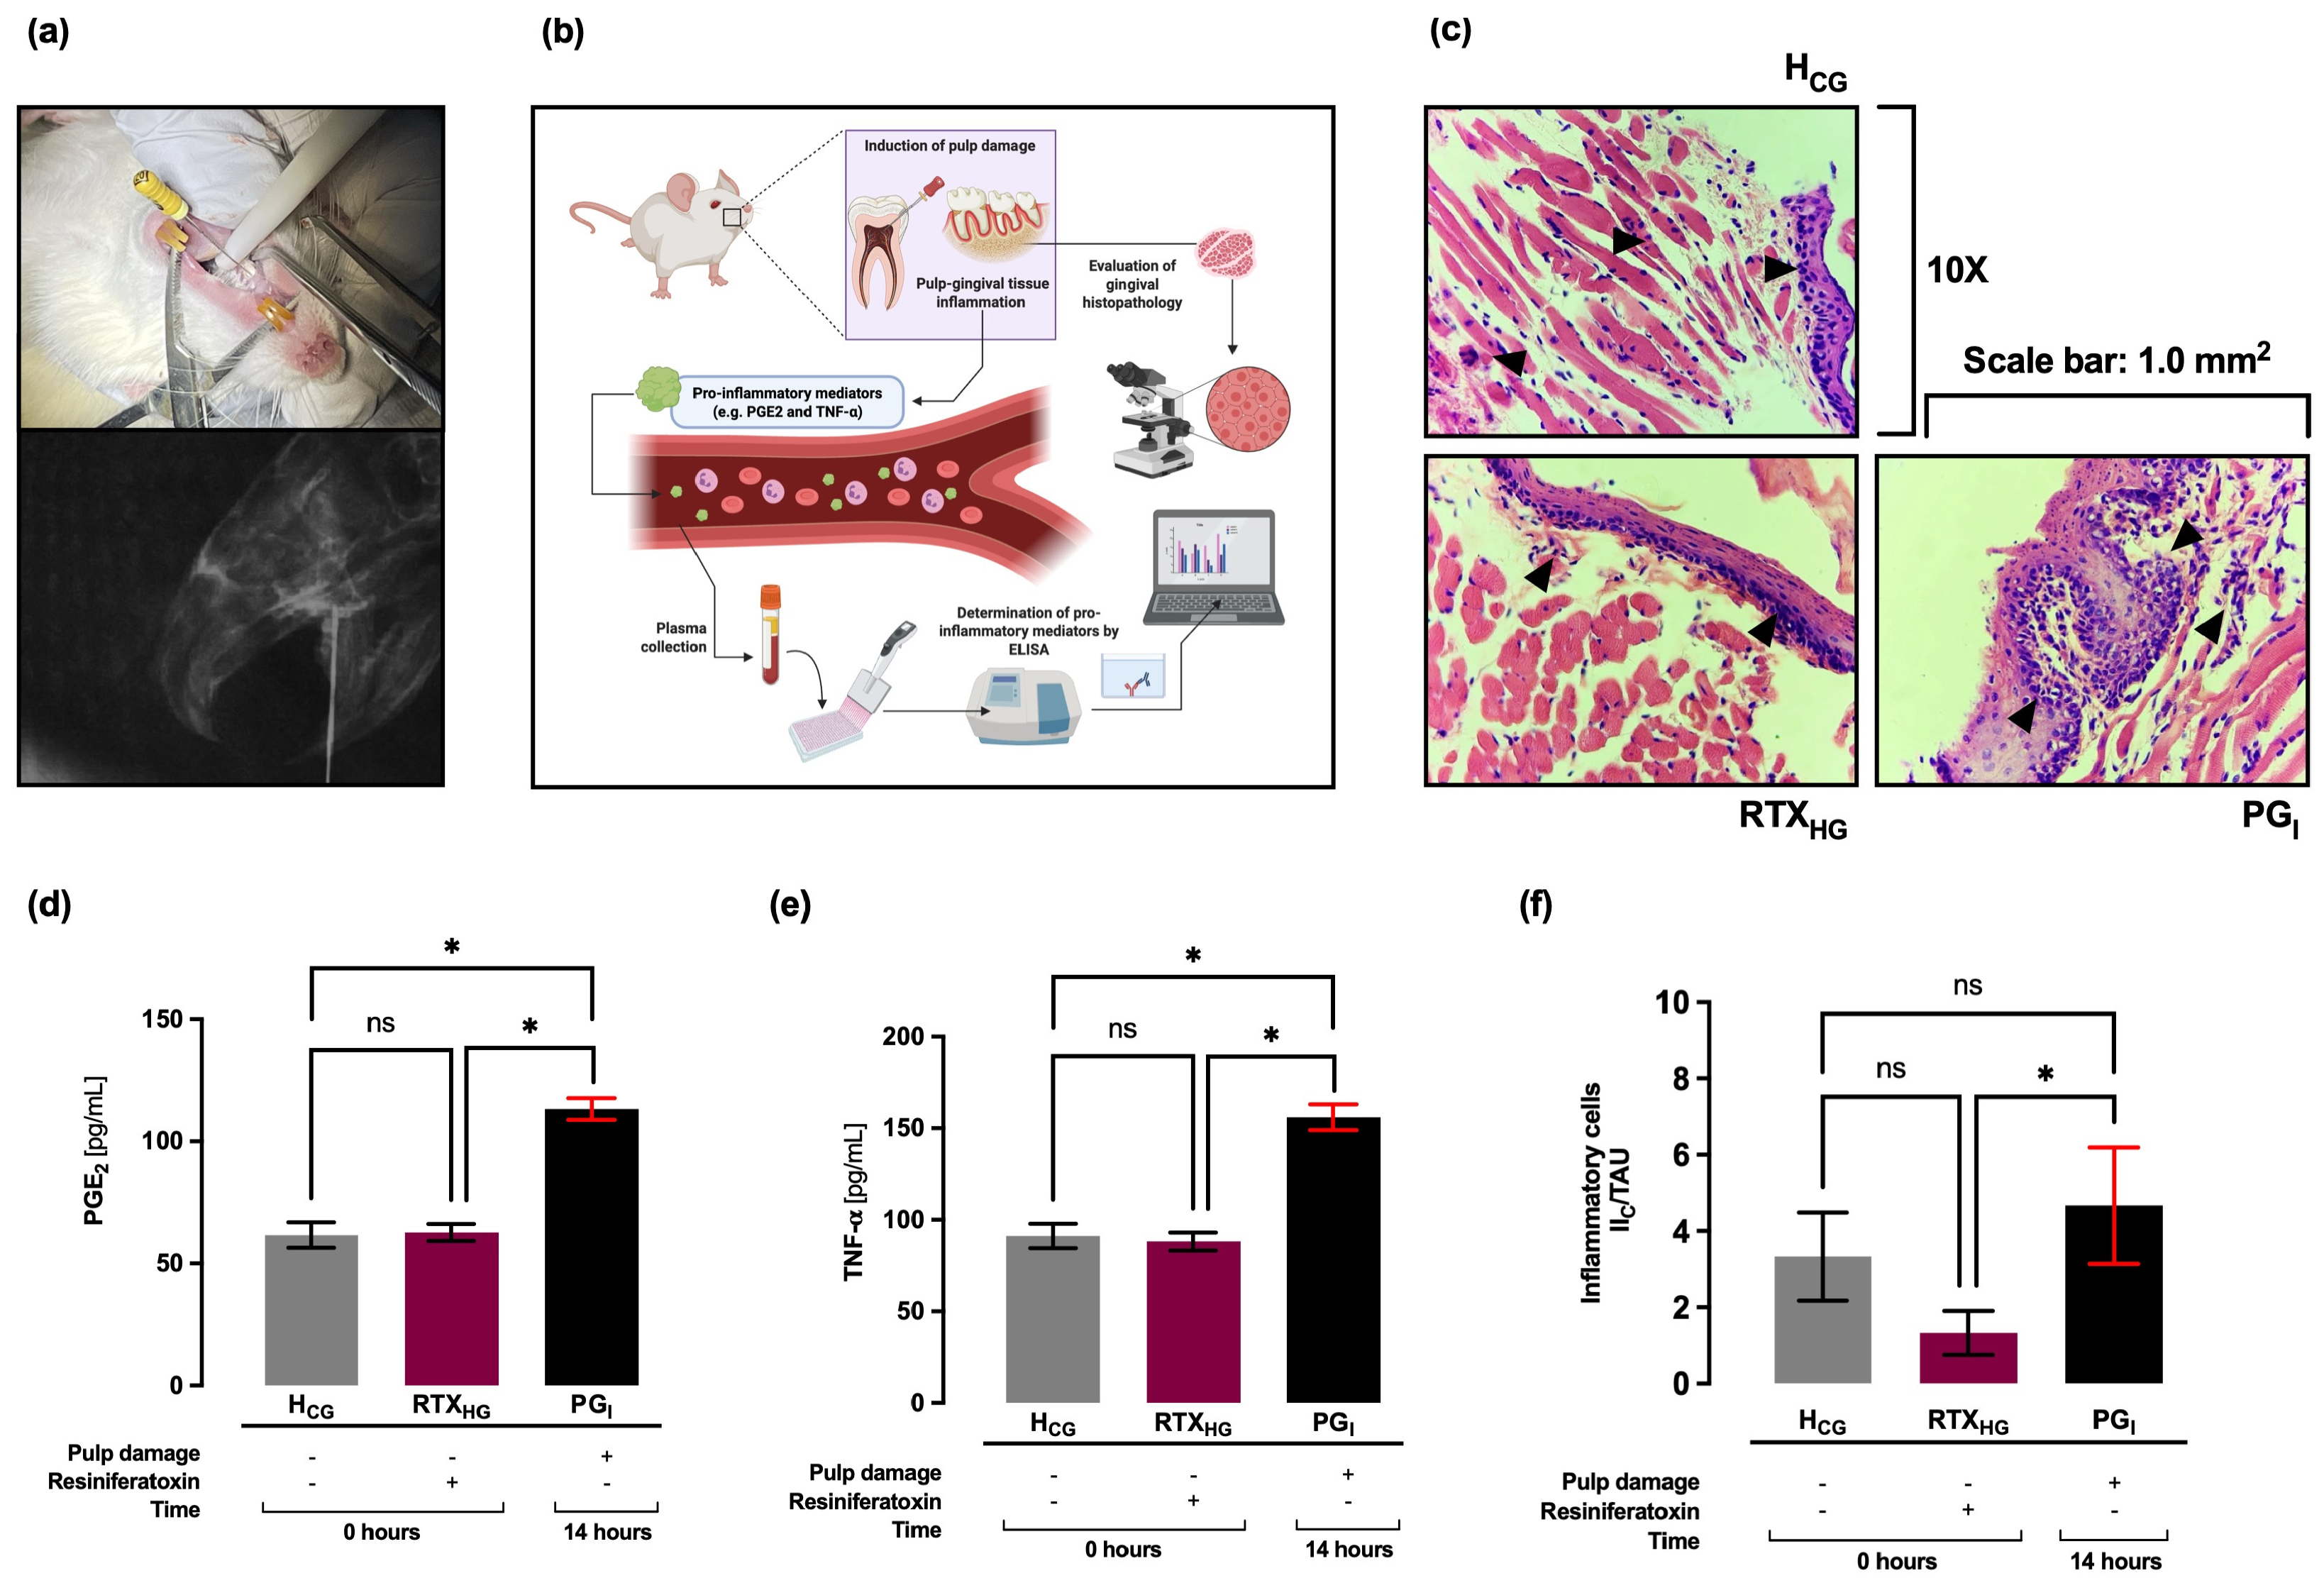
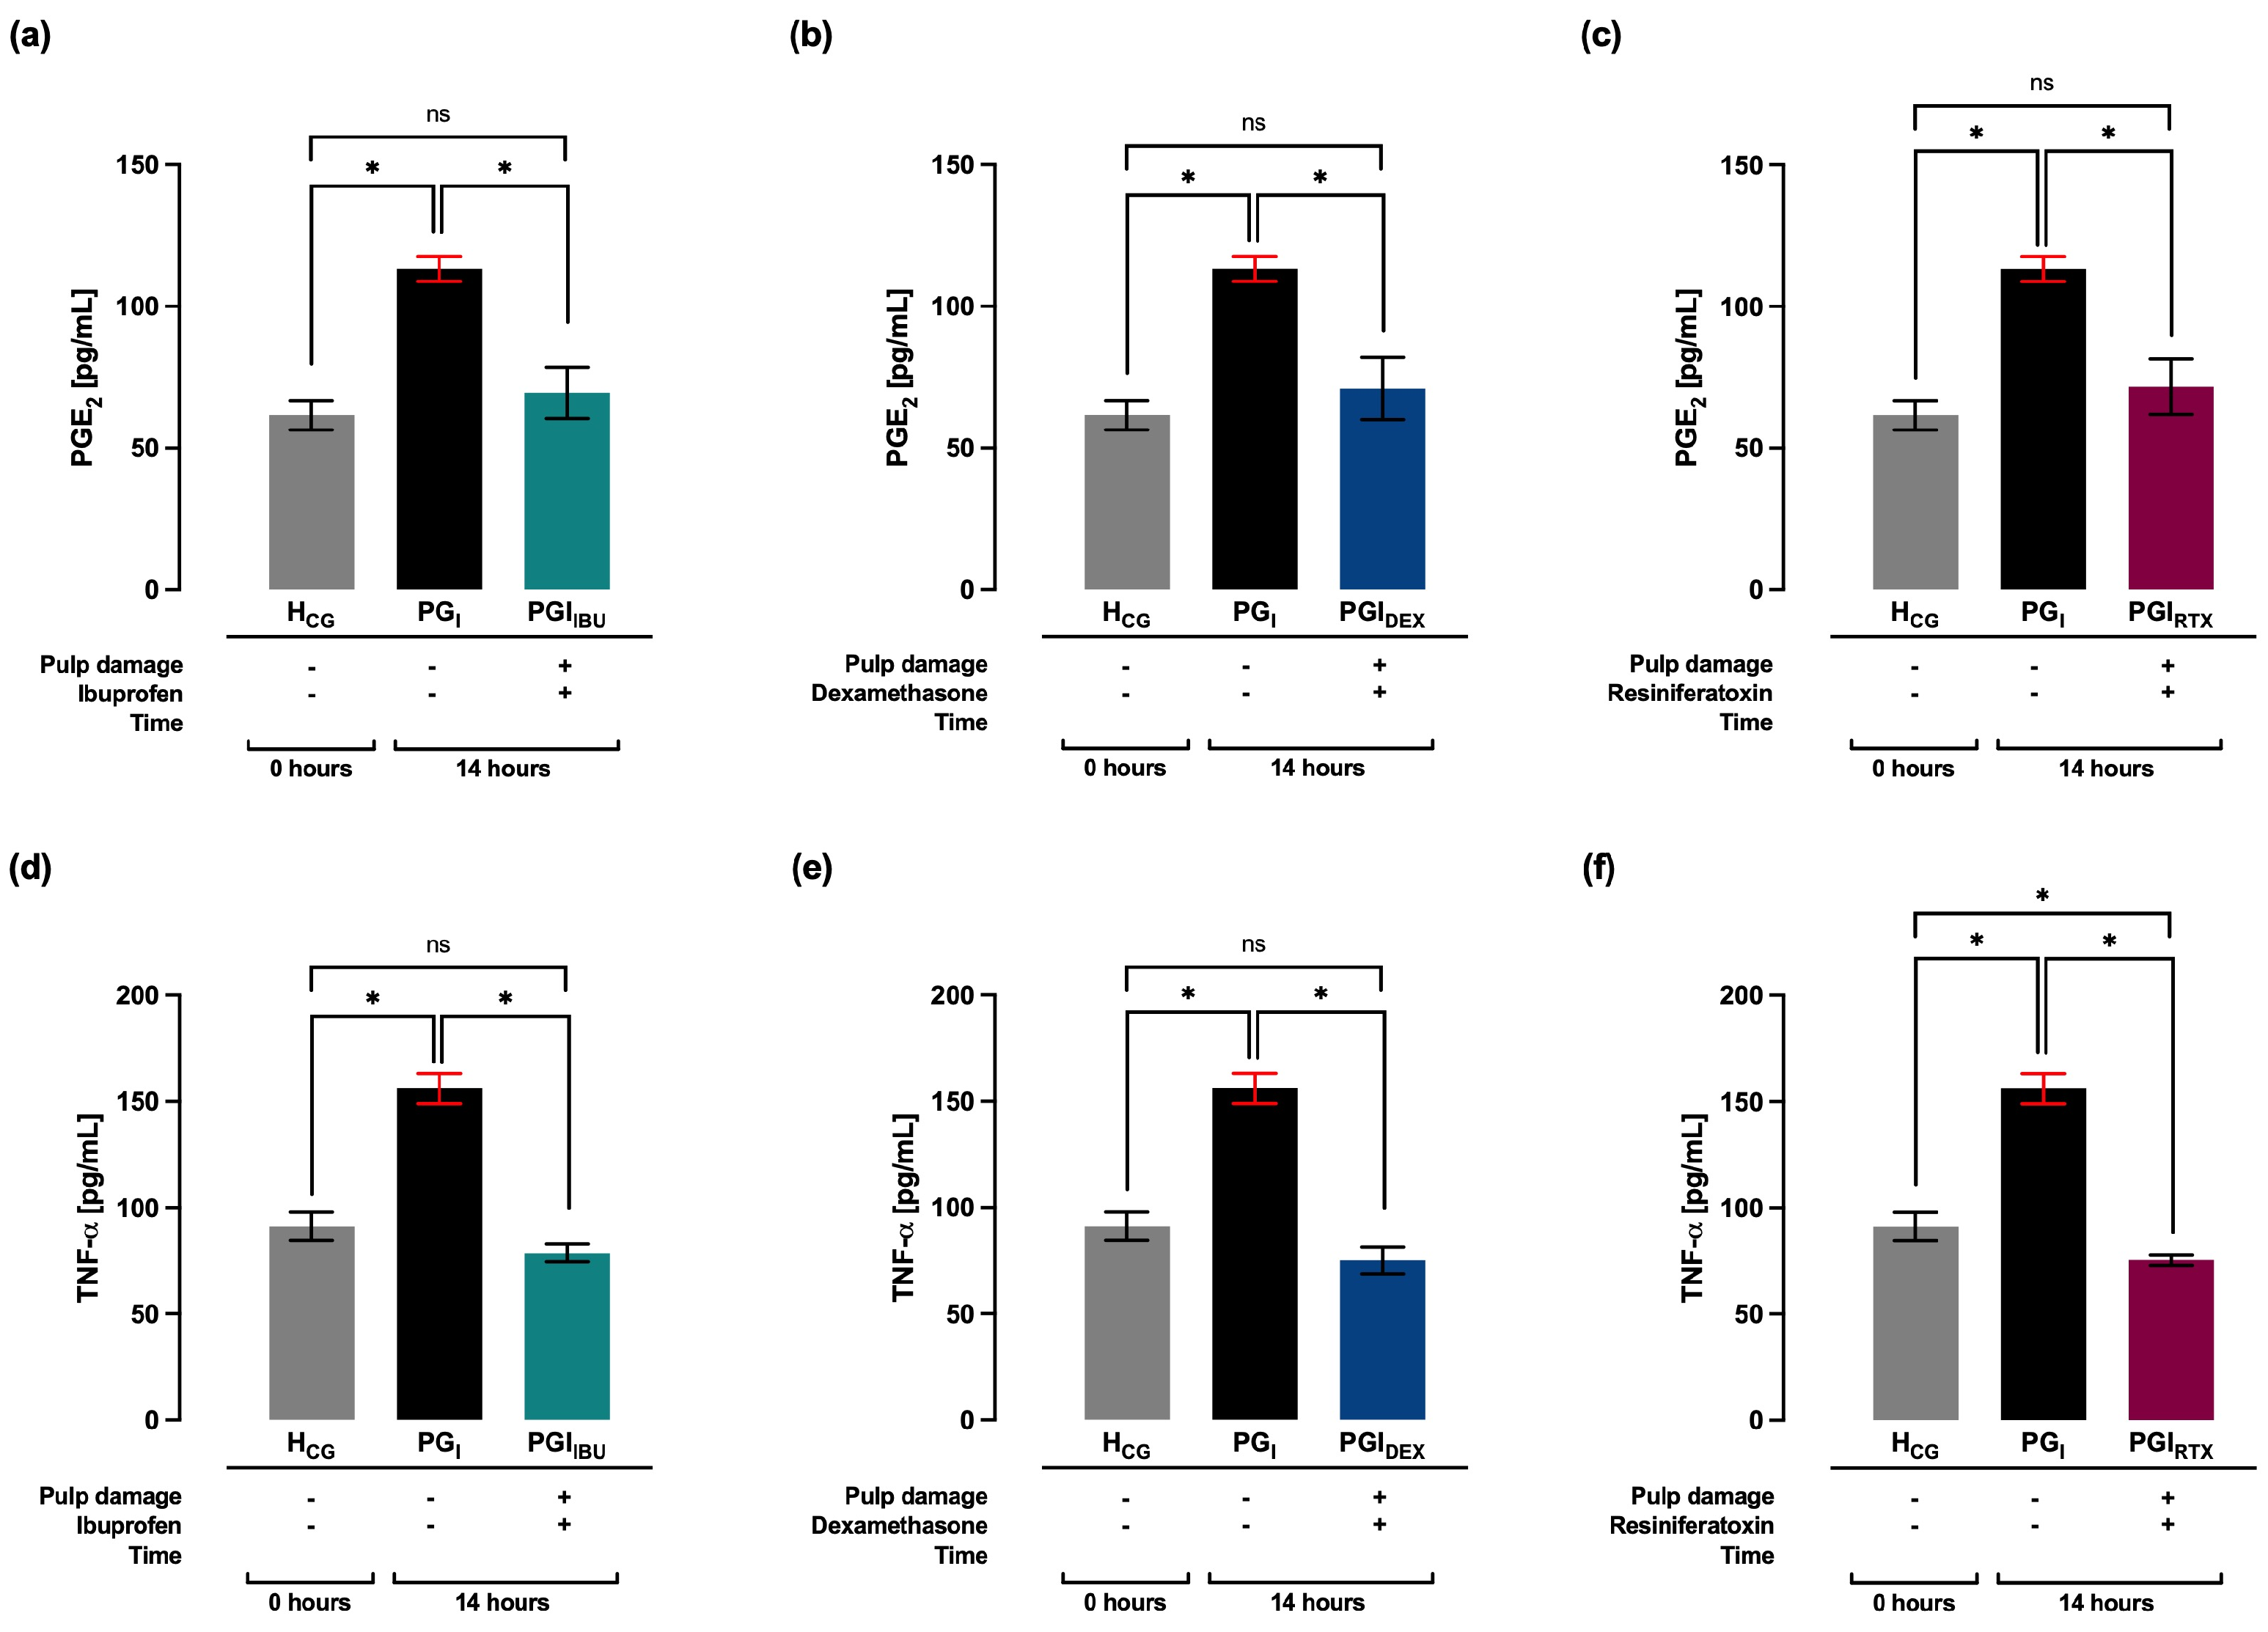
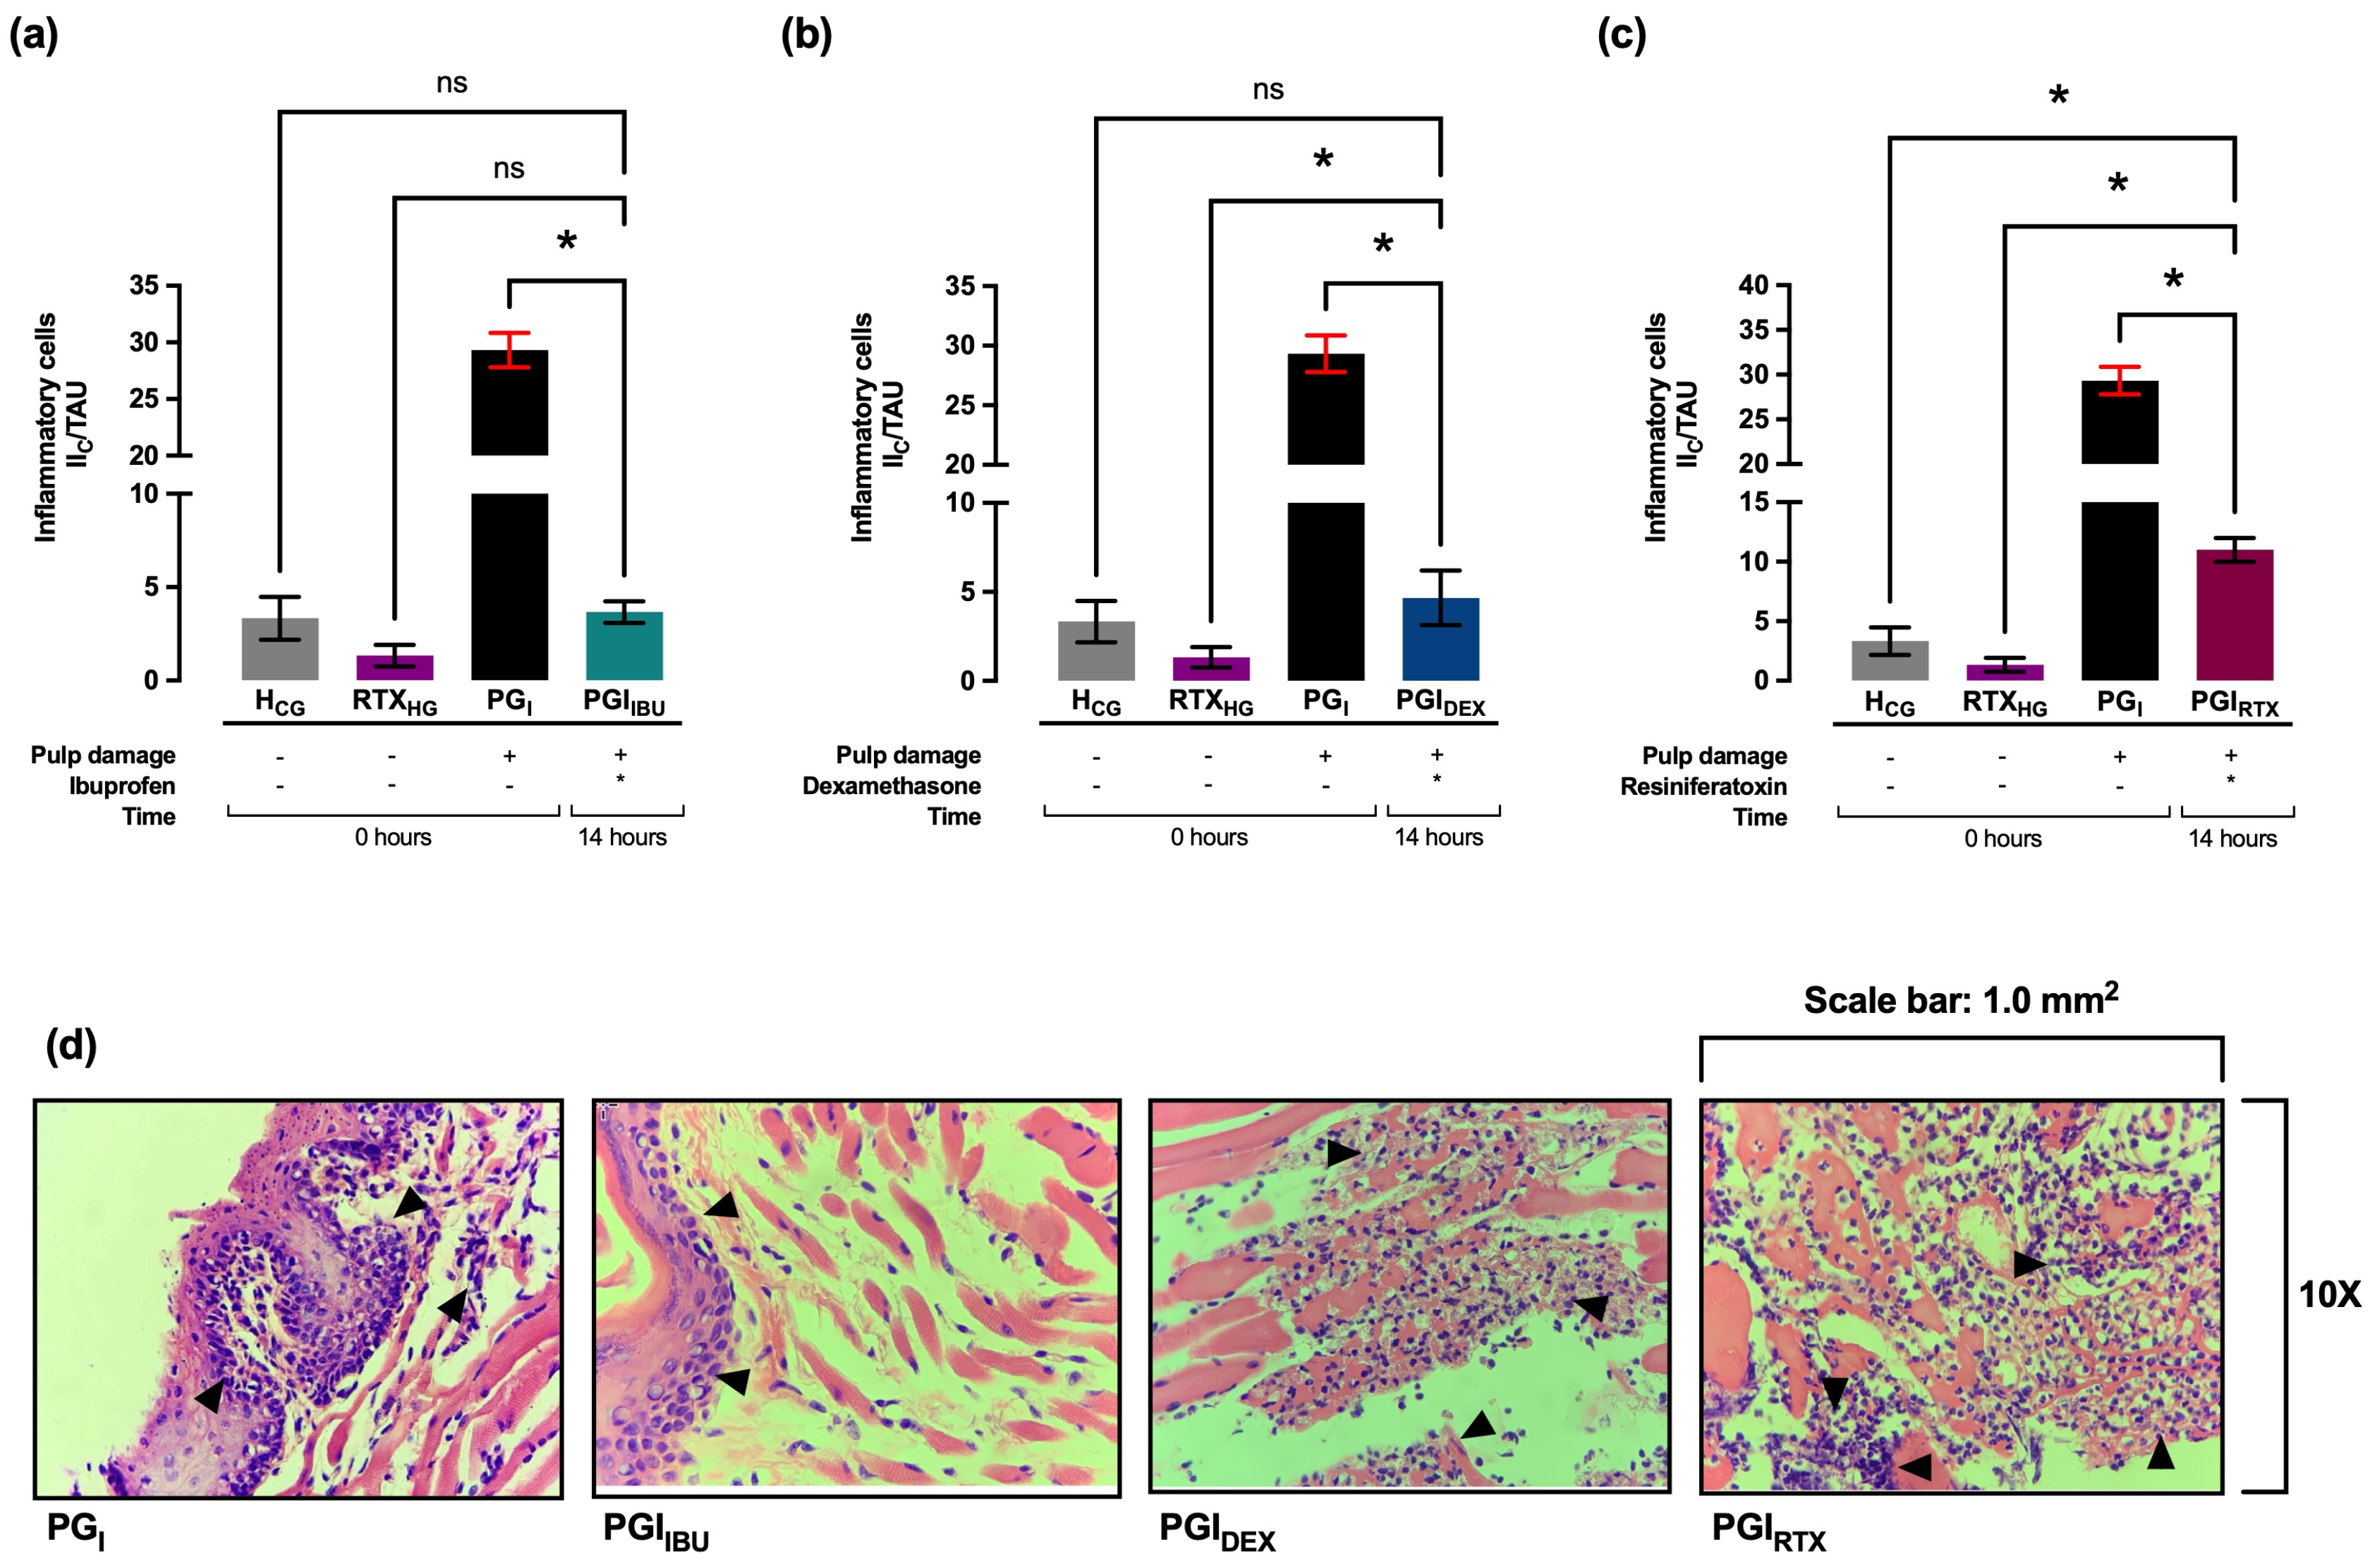
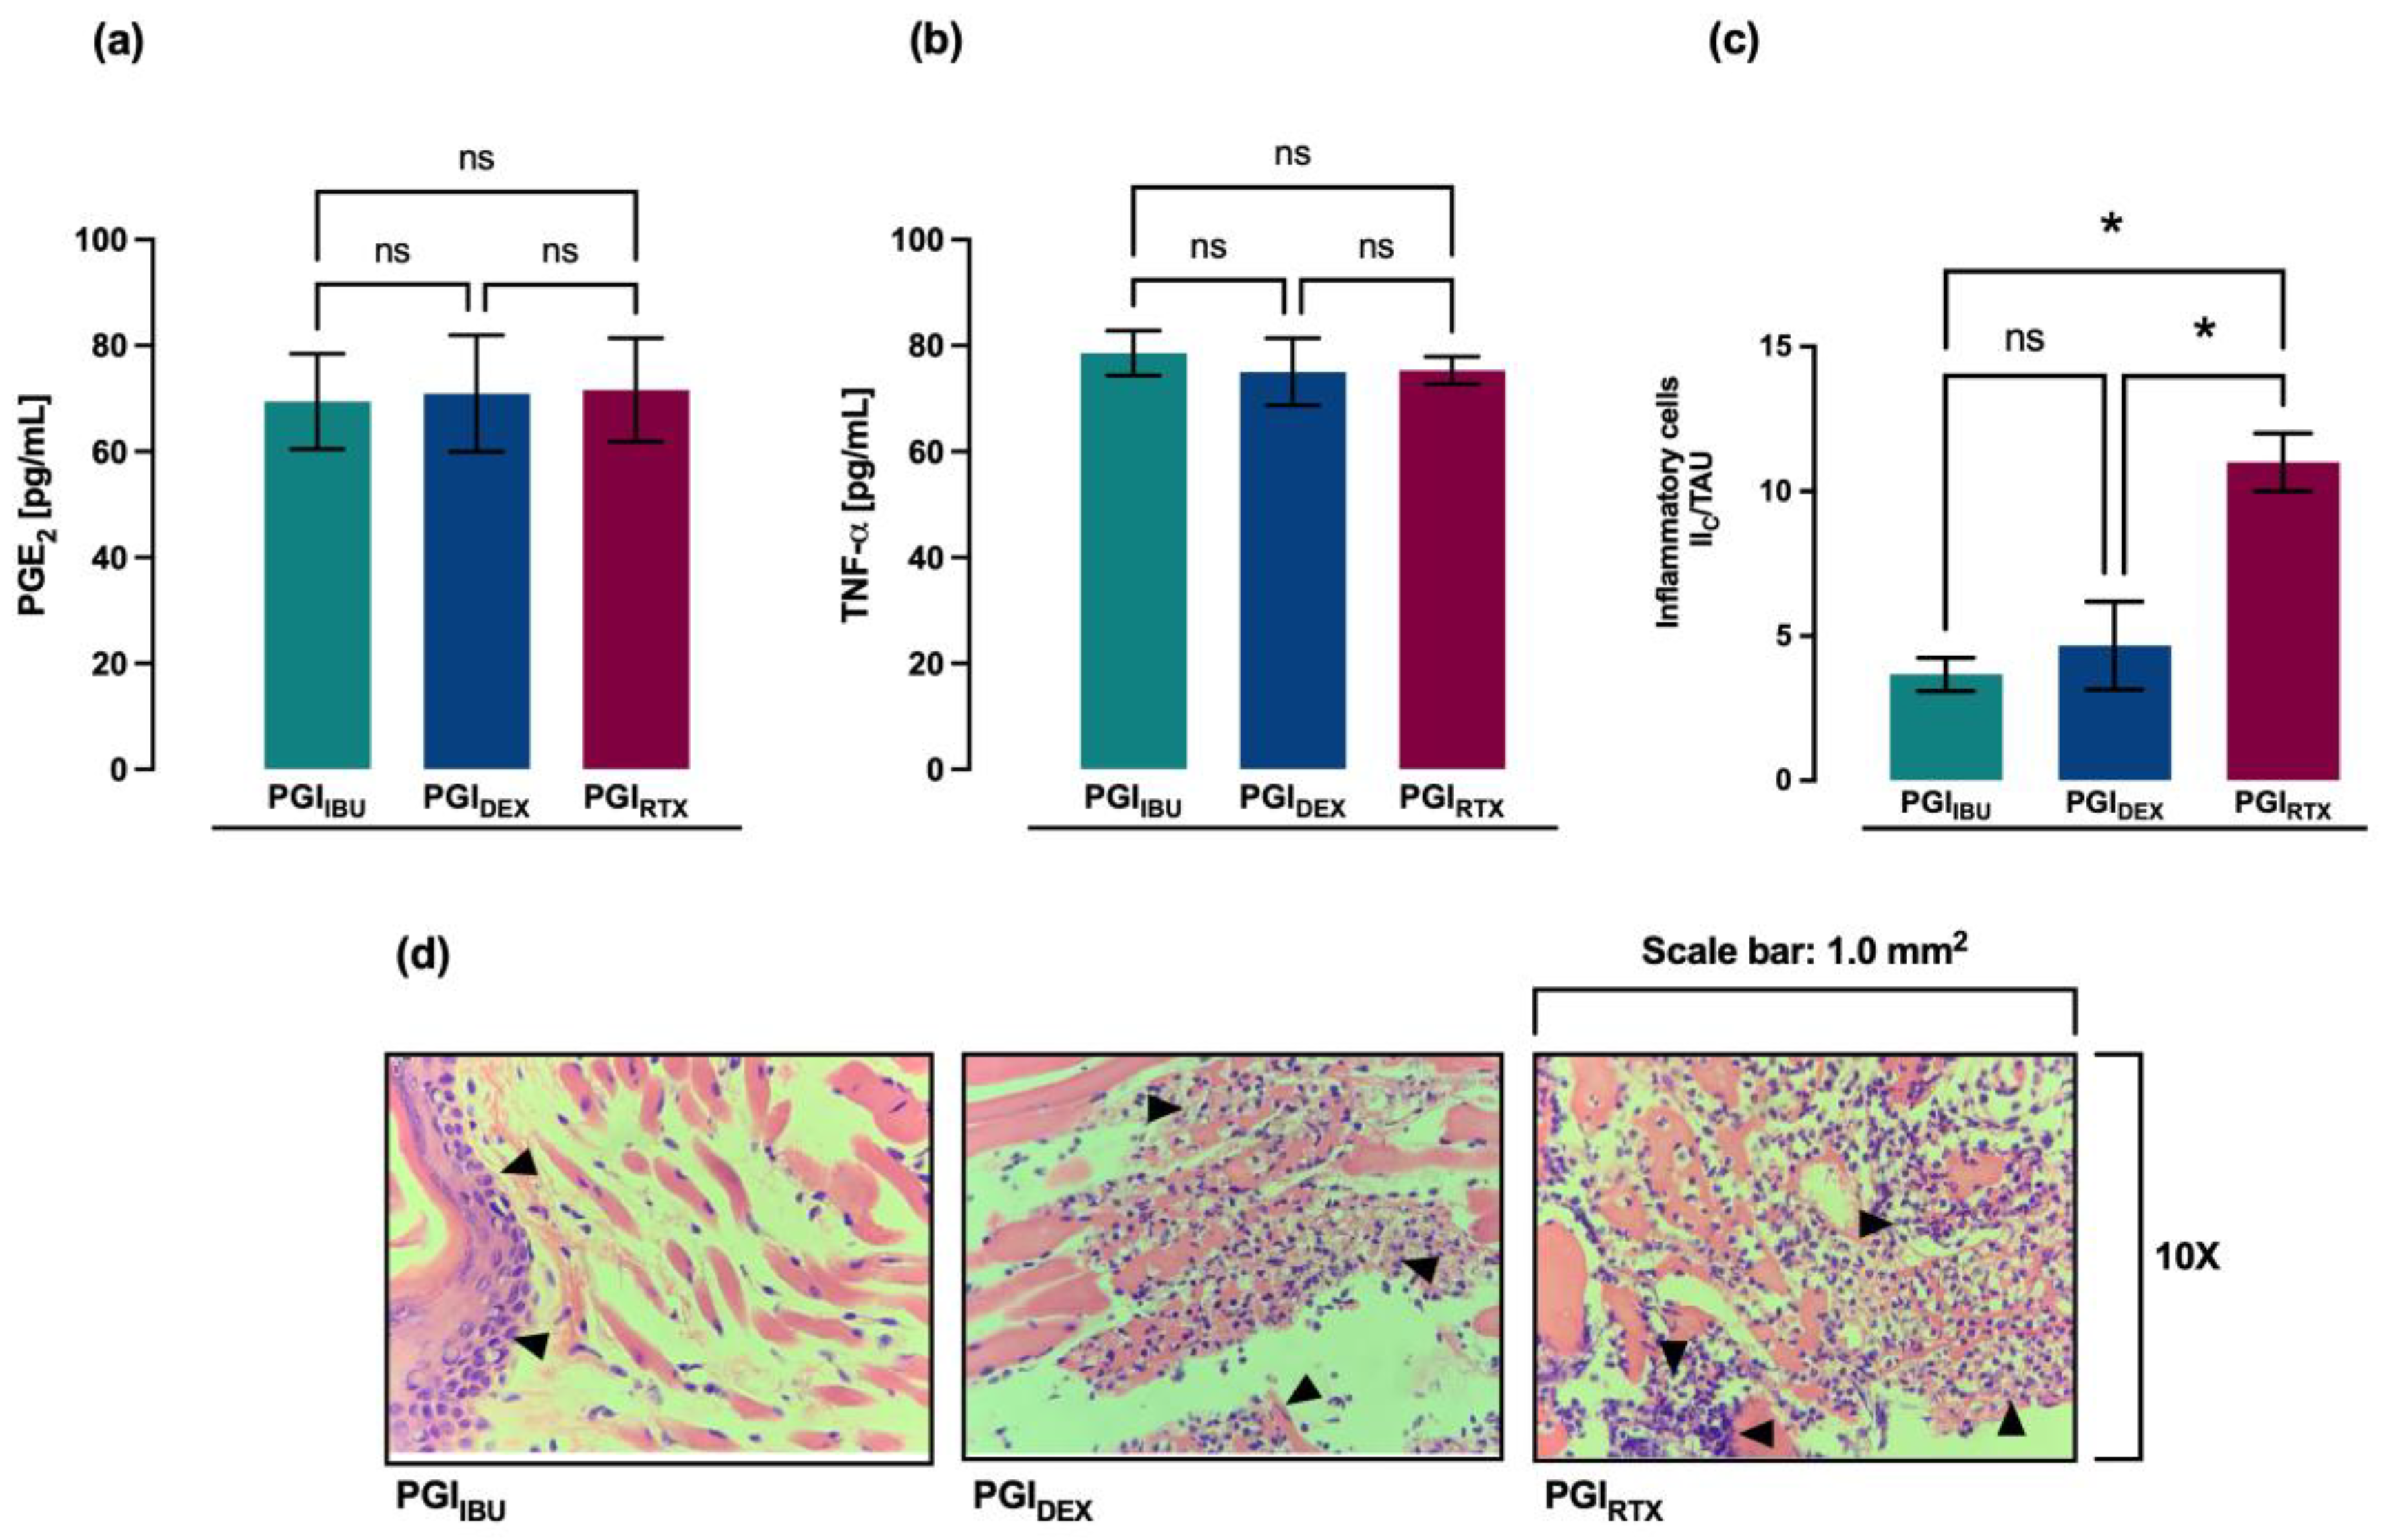

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.