


Abstract
Tetracyclines are broad-spectrum bacteriostatic agents with well-established antimicrobial efficacy and a shared core chemical structure, differentiated by distinct functional substitutions across generations. Beyond their antibacterial action, tetracyclines also exhibit pleiotropic biological effects, including modulation of bone metabolism. Nevertheless, the selection of agents and dosing for local bone applications remains largely empirical. Therefore, this study compares the tissue-level osteogenic potential of four tetracyclines from distinct generations using a translational ex vivo embryonic chick femur model. Organotypic femur cultures were maintained for 11 days and exposed to tetracycline (TC), doxycycline (DC), minocycline (MC), or sarecycline (SC), at 1 and 10 µg/mL, concentrations corresponding to clinically relevant local and systemic exposures. Osteogenic outcomes included microcomputed tomography, histological analyses, and quantitative gene expression. At 1 µg/mL, tetracyclines promoted osteogenic effects, increasing collagen deposition by approximately 30%, enhancing matrix maturation by 100%, stimulating tissue mineralization by 20–50%, and upregulating osteogenic marker expression, with TC exhibiting weaker activity. At 10 µg/mL, osteogenic stimulation was notably reduced across all groups. This study provides the first tissue-level, head-to-head comparison of four tetracyclines and their effects on bone biology. The findings indicate that tetracycline-induced osteogenic activity is both agent-specific and concentration-dependent, underscoring the importance of using lower doses to maximize osteogenic responses and supporting the preferential use of DC, MC, and SC in bone regeneration and adjunctive therapeutic applications.
1. Introduction
Tetracycline-class antibiotics are a group of broad-spectrum, bacteriostatic agents that have well-established efficacy against a wide range of Gram-positive and Gram-negative bacteria. Their antibacterial activity is achieved by reversibly binding to the 16S rRNA of the small 30S ribosomal subunit, preventing the attachment of aminoacyl-tRNA to the bacterial ribosome and ultimately suppressing bacterial growth [1,2].
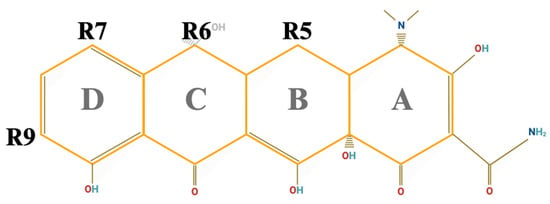
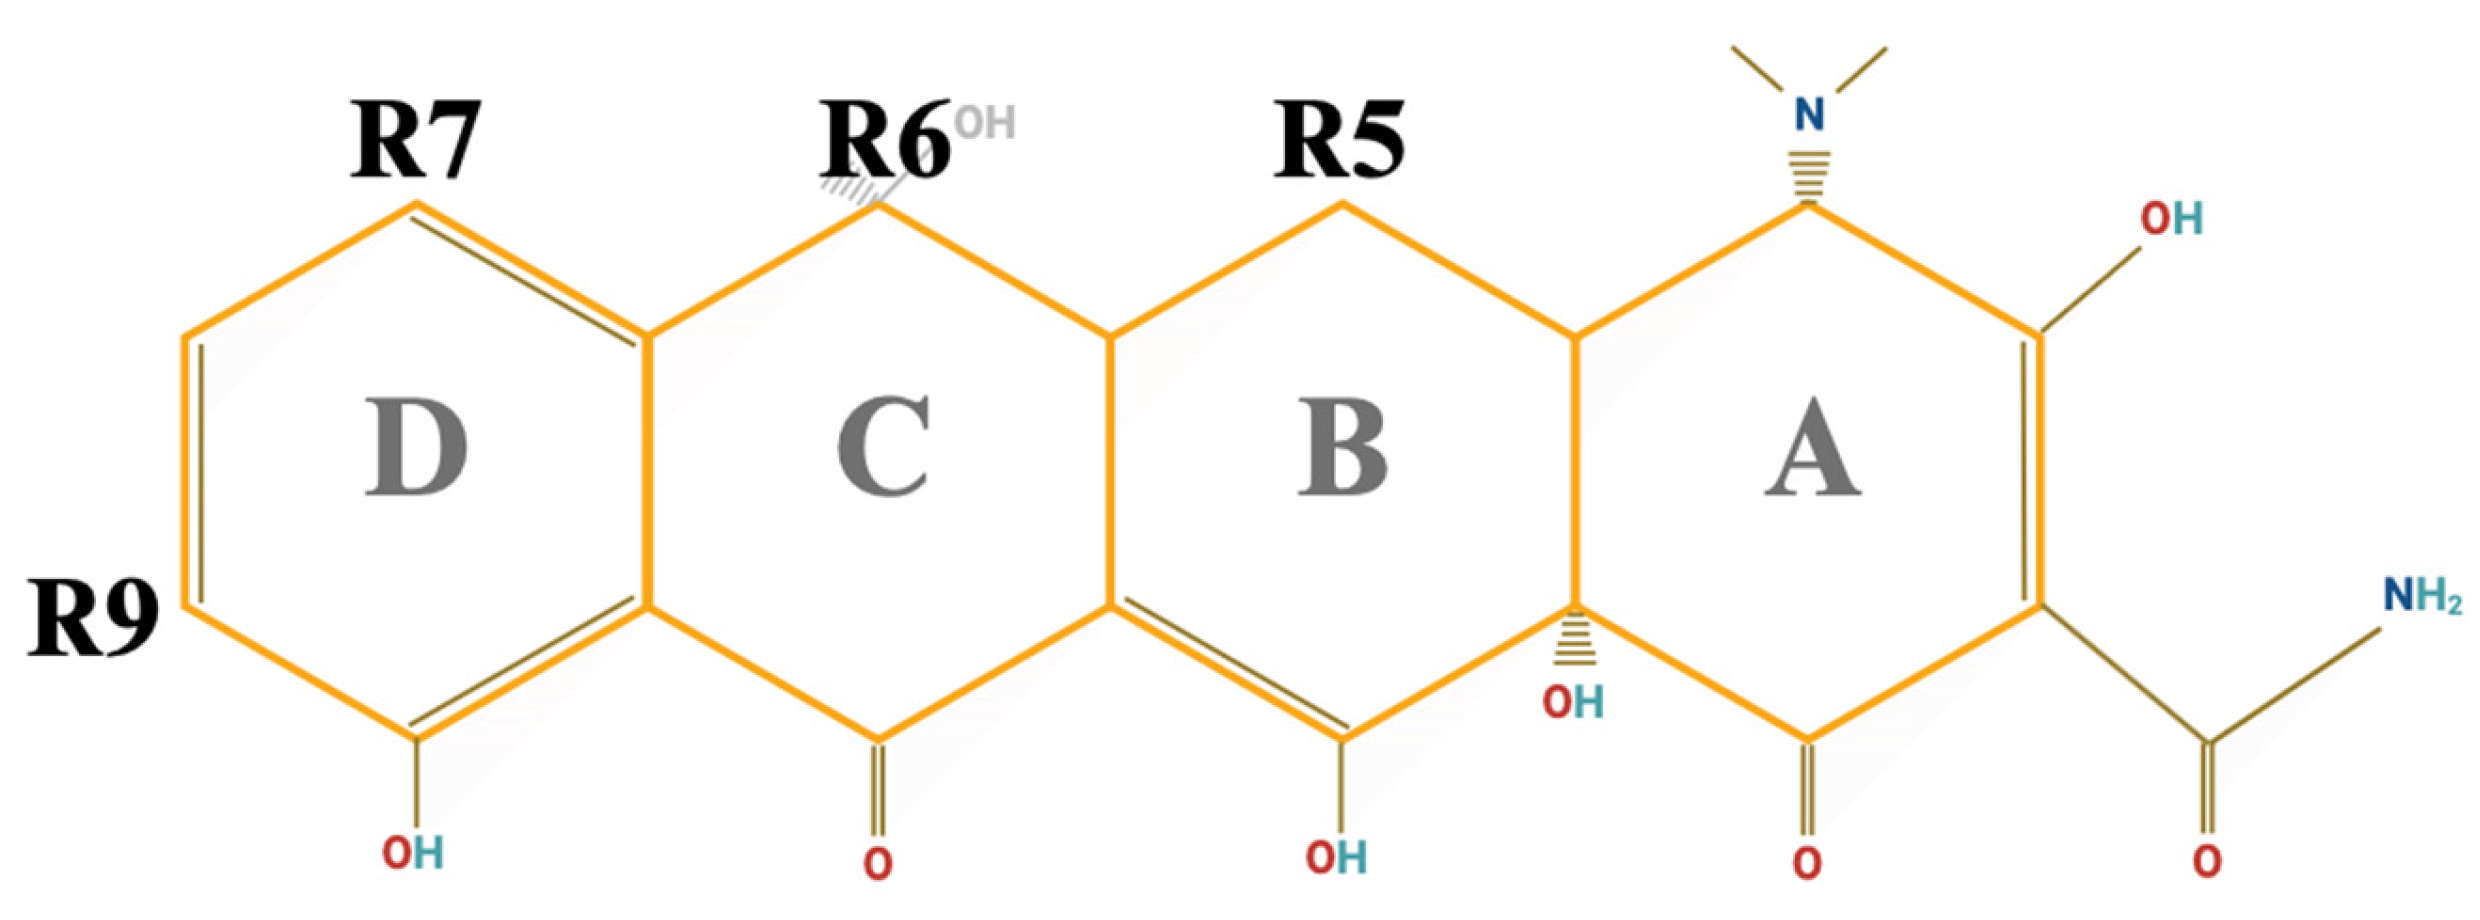
All tetracyclines share a core chemical structure of four linearly condensed aromatic rings (A, B, C, and D) arranged in a hydronaphthacene nucleus, distinguished by variations in functional groups attached to these rings (Figure 1). The key sites of structural optimization are the R5, R6, R7, and R9 positions, which also guide their classification into three generations [1]. First-generation compounds, such as tetracycline, underwent initial modifications to enhance their pharmacological profile and oral bioavailability, particularly by improving water solubility and plasma protein binding. These refinements led to the development of second-generation derivatives, represented by doxycycline and minocycline. Relative to tetracycline, doxycycline features subtle modifications at R5 and R6, involving the replacement of a hydrogen with a hydroxyl group at R5 and the loss of a hydroxyl group at R6. In contrast, minocycline exhibits alterations at R6 and R7, characterized by the removal of methyl and hydroxyl groups at R6 and the introduction of a dimethylamino substituent at R7 [3,4].
Figure 1.
Chemical structure of tetracycline highlighting the primary positions targeted for structural optimization (R5, R6, R7, and R9).
Third-generation tetracyclines are derived from the minocycline structure, and two distinct development strategies were pursued. On one hand, tigecycline, omadacycline, and eravacycline were designed to overcome bacterial resistance mechanisms by incorporating distinct functional groups at the R9 position, thereby increasing their binding affinity to the ribosomal 30S subunit target. Tigecycline incorporates a glycylamido side chain at R9, omadacycline features an aminomethyl group at R9, while eravacycline includes a pyrrolidinoacetamido group at R9 with an additional substitution (i.e., fluorine) at R7 [3,4,5]. Sarecycline, on the other hand, was optimized specifically for acne management, featuring a unique R7 modification (i.e., methoxy(methyl) amino-methyl) that narrows the antibacterial spectrum primarily to dermatologically relevant Gram-positive bacteria while limiting blood–brain penetration. As a result, sarecycline exhibits a reduced risk of inducing bacterial resistance, disturbing the intestinal microbiota, or causing other adverse effects [5,6].
Beyond their antimicrobial properties, tetracyclines are under investigation for the management of noninfectious conditions owing to their pleiotropic effects, including inhibition of matrix metalloproteinases (MMPs), antioxidant, anti-inflammatory, and bone-modulating activities [1,2,7]. These features have prompted their potential use in diverse clinical applications, including cancer therapy, the management of neurological disorders, osteoimmunoinflammatory conditions, and bone regeneration [8], and have already led to the commercialization of sub-antimicrobial formulations for dermatological indications and adjunctive anti-enzymatic therapies for periodontitis (e.g., Oracea®, Periostat®). Furthermore, local delivery platforms have been explored as advanced therapeutic strategies, enabling targeted tetracycline release with reduced systemic exposure [4]. Nevertheless, the selection of specific agents and concentration ranges, particularly for in situ applications, remains largely empirical. Given the critical role of structural modifications in determining therapeutic actions, further research is warranted to optimize the selection of specific agents for distinct clinical applications.
Importantly, tetracyclines have a unique relationship with mineralized tissues, making their effects on bone biology particularly relevant. In bone tissue, tetracyclines exhibit a strong affinity for the mineralized matrix through calcium chelation [6,9]. Consequently, their use during pregnancy or in pediatric patients can impair skeletal and tooth development [10]. Conversely, in post-development contexts, tetracyclines display beneficial effects, particularly in bone defect repair and periodontal therapy [11,12,13]. Mechanistically, they appear to exert strong anti-osteoclastogenic effects by inhibiting osteoclast formation and inducing apoptosis, thereby suppressing resorptive activity, primarily by inhibiting RANKL-induced MMP-9 activity and NFATc1 signaling [14,15]. Additionally, evidence suggests that tetracyclines stimulate osteoblastic activity, although their pro-osteoblastogenic effects remain underexplored. Preliminary data suggest that different tetracycline derivatives exert divergent, dose-dependent effects on osteoblastic cells and may promote osteogenic commitment through activation of distinct signaling pathways [6,16,17]. However, the extent to which structural modifications across tetracycline generations translate into distinct bone responses remains poorly understood.
Previously, our research group assessed the in vitro osteogenic potential of tetracycline (first generation), doxycycline, minocycline (second generation), and sarecycline (third generation) in human bone marrow mesenchymal stem cells, focusing on their impact on osteogenic signaling pathways and functional activity [16]. As observed, tetracycline and doxycycline primarily activated the Wnt pathway, whereas minocycline and sarecycline mainly upregulated Hedgehog signaling, a profile associated with a more pronounced osteogenic induction. Building upon these findings, the present study advances the evaluation from the cellular to the tissue level by employing an ex vivo organotypic bone model that preserves the native three-dimensional architecture of the bone matrix and sustains physiologically relevant cell–cell and cell–matrix interactions [18]. This model, characterized by its high responsiveness to external stimuli, enables a comprehensive comparison of tetracycline agents and a detailed assessment of their effects on tissue microarchitecture, including collagen deposition, collagen maturation, and extracellular matrix mineralization [19,20]. By overcoming the physiological relevance of conventional in vitro assays and circumventing the ethical, biological, and interpretative complexities of in vivo studies, this approach provides a robust translational platform to dissect the tissue-level actions of tetracyclines on bone. Therefore, in this study, the ex vivo femora model was employed to systematically evaluate and compare the effects of tetracycline, doxycycline, minocycline, and sarecycline on bone tissue dynamics, thereby addressing the knowledge gap regarding how structural differences among tetracyclines shape bone responses.
2. Results
2.1. Linear Growth and Volumetric Bone Analysis
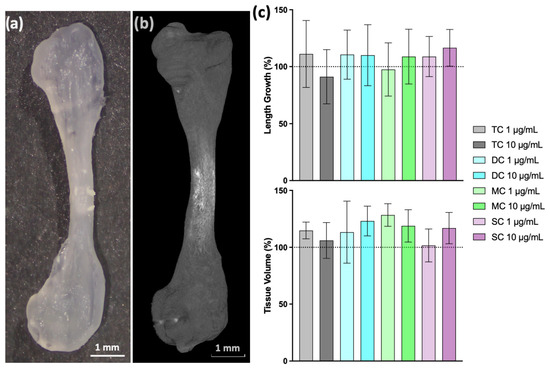
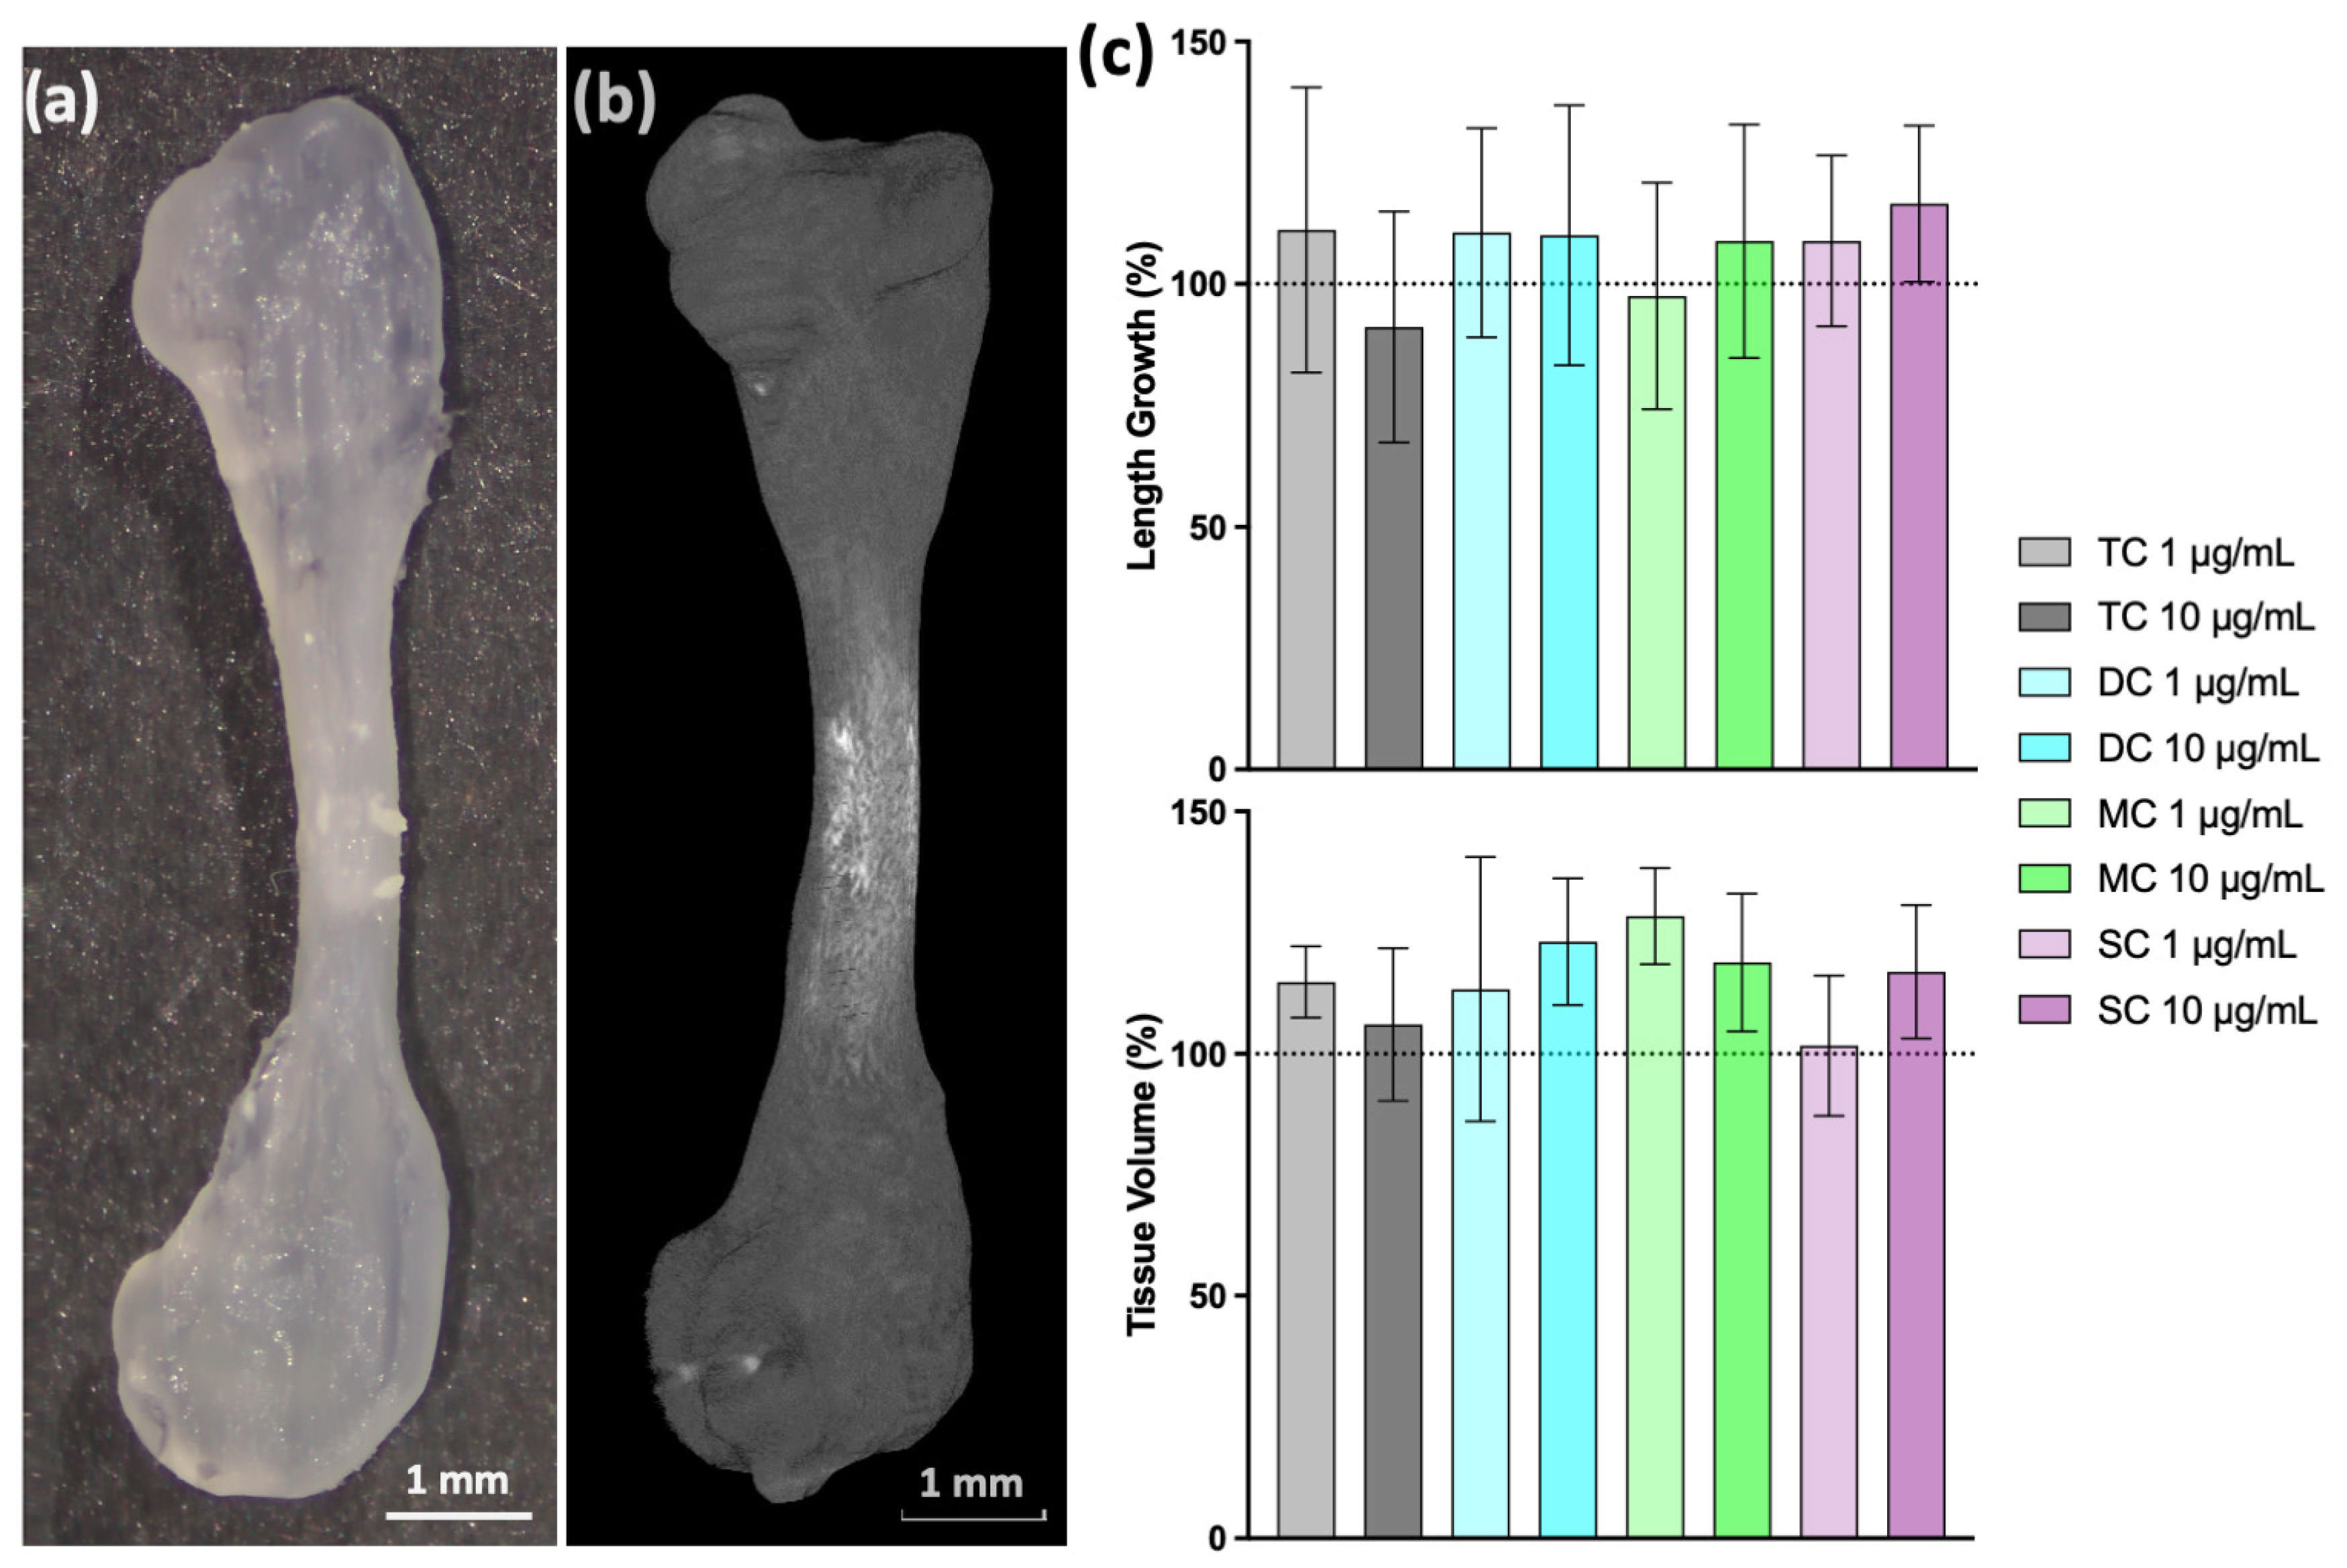
To assess the impact of tetracycline exposure on femoral development, overall morphology, linear growth, and tissue structure were examined at baseline and after 11 days of culture. Representative macrographs (Figure 2a) and microtomographic reconstructions (Figure 2b) showed no apparent differences in overall bone architecture between experimental groups and controls. Longitudinal measurements confirmed that femoral length increased by approximately 4 mm in both control and experimental groups, with no significant differences observed (Figure 2c). Similarly, 3D quantitative morphometric analysis of total femoral volume (Figure 2c) revealed only a minor, non-significant increase in most experimental groups as compared to controls.
Figure 2.
Representative images of the ex vivo-cultured chick femur after 11 days of incubation (a) and corresponding three-dimensional reconstruction (b) from the control group. (c) Upper graph—Quantitative analysis of longitudinal growth (final vs. initial femoral length). Lower graph—Microtomographic evaluation of total femoral volume. Results are normalized to the control group, set as 100%, represented by the dashed line. No statistically significant differences were found (n = 5, p ≤ 0.05). For reference, the absolute growth values (in mm) are as follows: Control–3.95; TC 1 µg/mL–4.39; TC 10 µg/mL–3.6; DC 1 µg/mL–4.36; DC 10 µg/mL–4.34; MC 1 µg/mL–3.85; MC 10 µg/mL–4.29; SC 1 µg/mL–4.3; SC 10 µg/mL–4.6. For reference, the absolute tissue volume values, expressed in mm3, are as follows: Control–12.25; TC 1 µg/mL–14.07; TC 10 µg/mL–12.99; DC 1 µg/mL–13.88; DC 10 µg/mL–15.06; MC 1 µg/mL–15.73; MC 10 µg/mL–14.56; SC 1 µg/mL–12.45; SC 10 µg/mL–15.55.
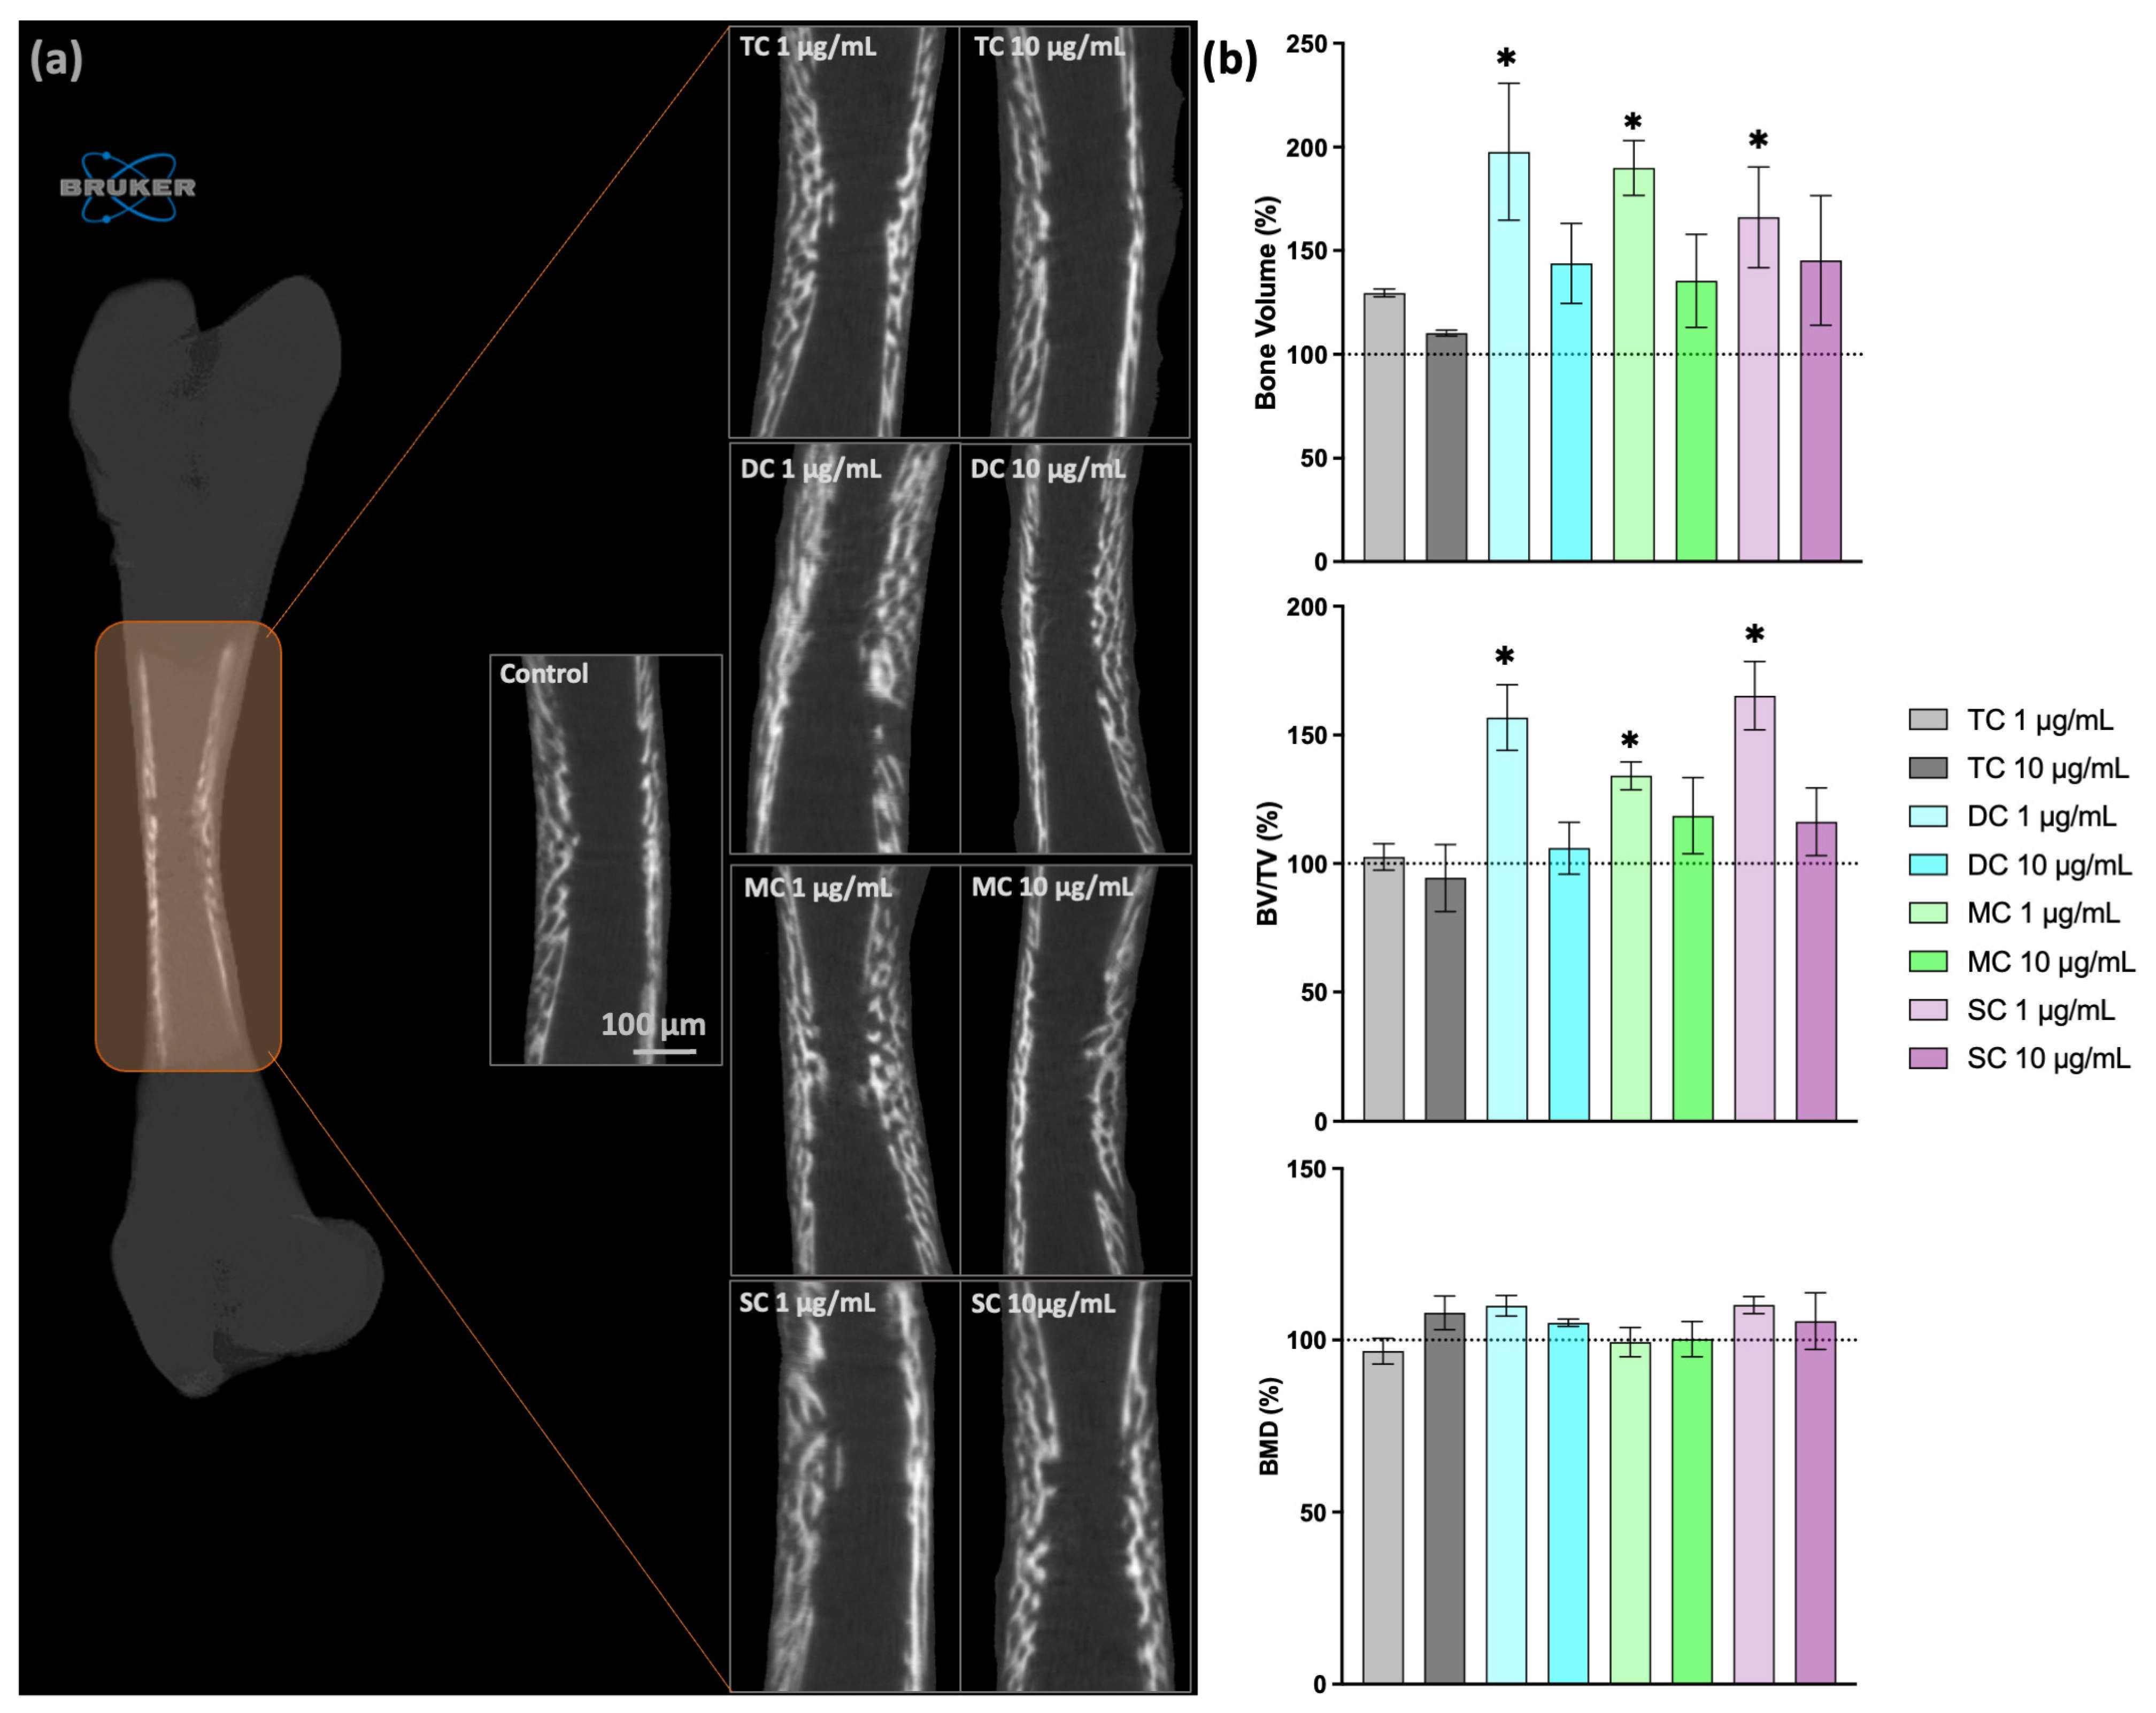
3D reconstructions of sagittal sections centered on the diaphyseal region, along with quantitative morphometric analyses of mineralized tissue, are shown in Figure 3. Control femora displayed mineralized tissue organized in developing trabeculae, extending from the peripheral regions into the interior, most prominently within the mid-diaphyseal area. Tetracycline-exposed groups exhibited visibly thicker bone walls and a trend toward increased mineralization of trabecular structures within the innermost diaphyseal region. The quantitative analysis supports the observed findings: at 1 µg/mL, all tetracyclines except TC significantly increased bone volume and bone volume fraction in comparison to the control. No significant differences were observed at 10 µg/mL for any compound. Bone mineral density (BMD) remained unchanged across all groups, regardless of the tetracycline type or concentration.
Figure 3.
Representative images of three-dimensional reconstruction of the sagittal femoral diaphyseal area (a) and quantitative histomorphometric analysis of mineralized tissue (b). Results are normalized to the control group, set as 100%, represented by the dashed line (*), different from the control. (n = 5, p ≤ 0.05). For reference, the absolute bone volume values, expressed in mm3, are as follows: Control–0.144; TC 1 µg/mL–0.187; TC 10 µg/mL–0.159; DC 1 µg/mL–0.286; DC 10 µg/mL–0.2; MC 1 µg/mL–0.275; MC 10 µg/mL–0.225; SC 1 µg/mL–0.267; SC 10 µg/mL–0.22.
2.2. Histological and Histomorphometric Analysis
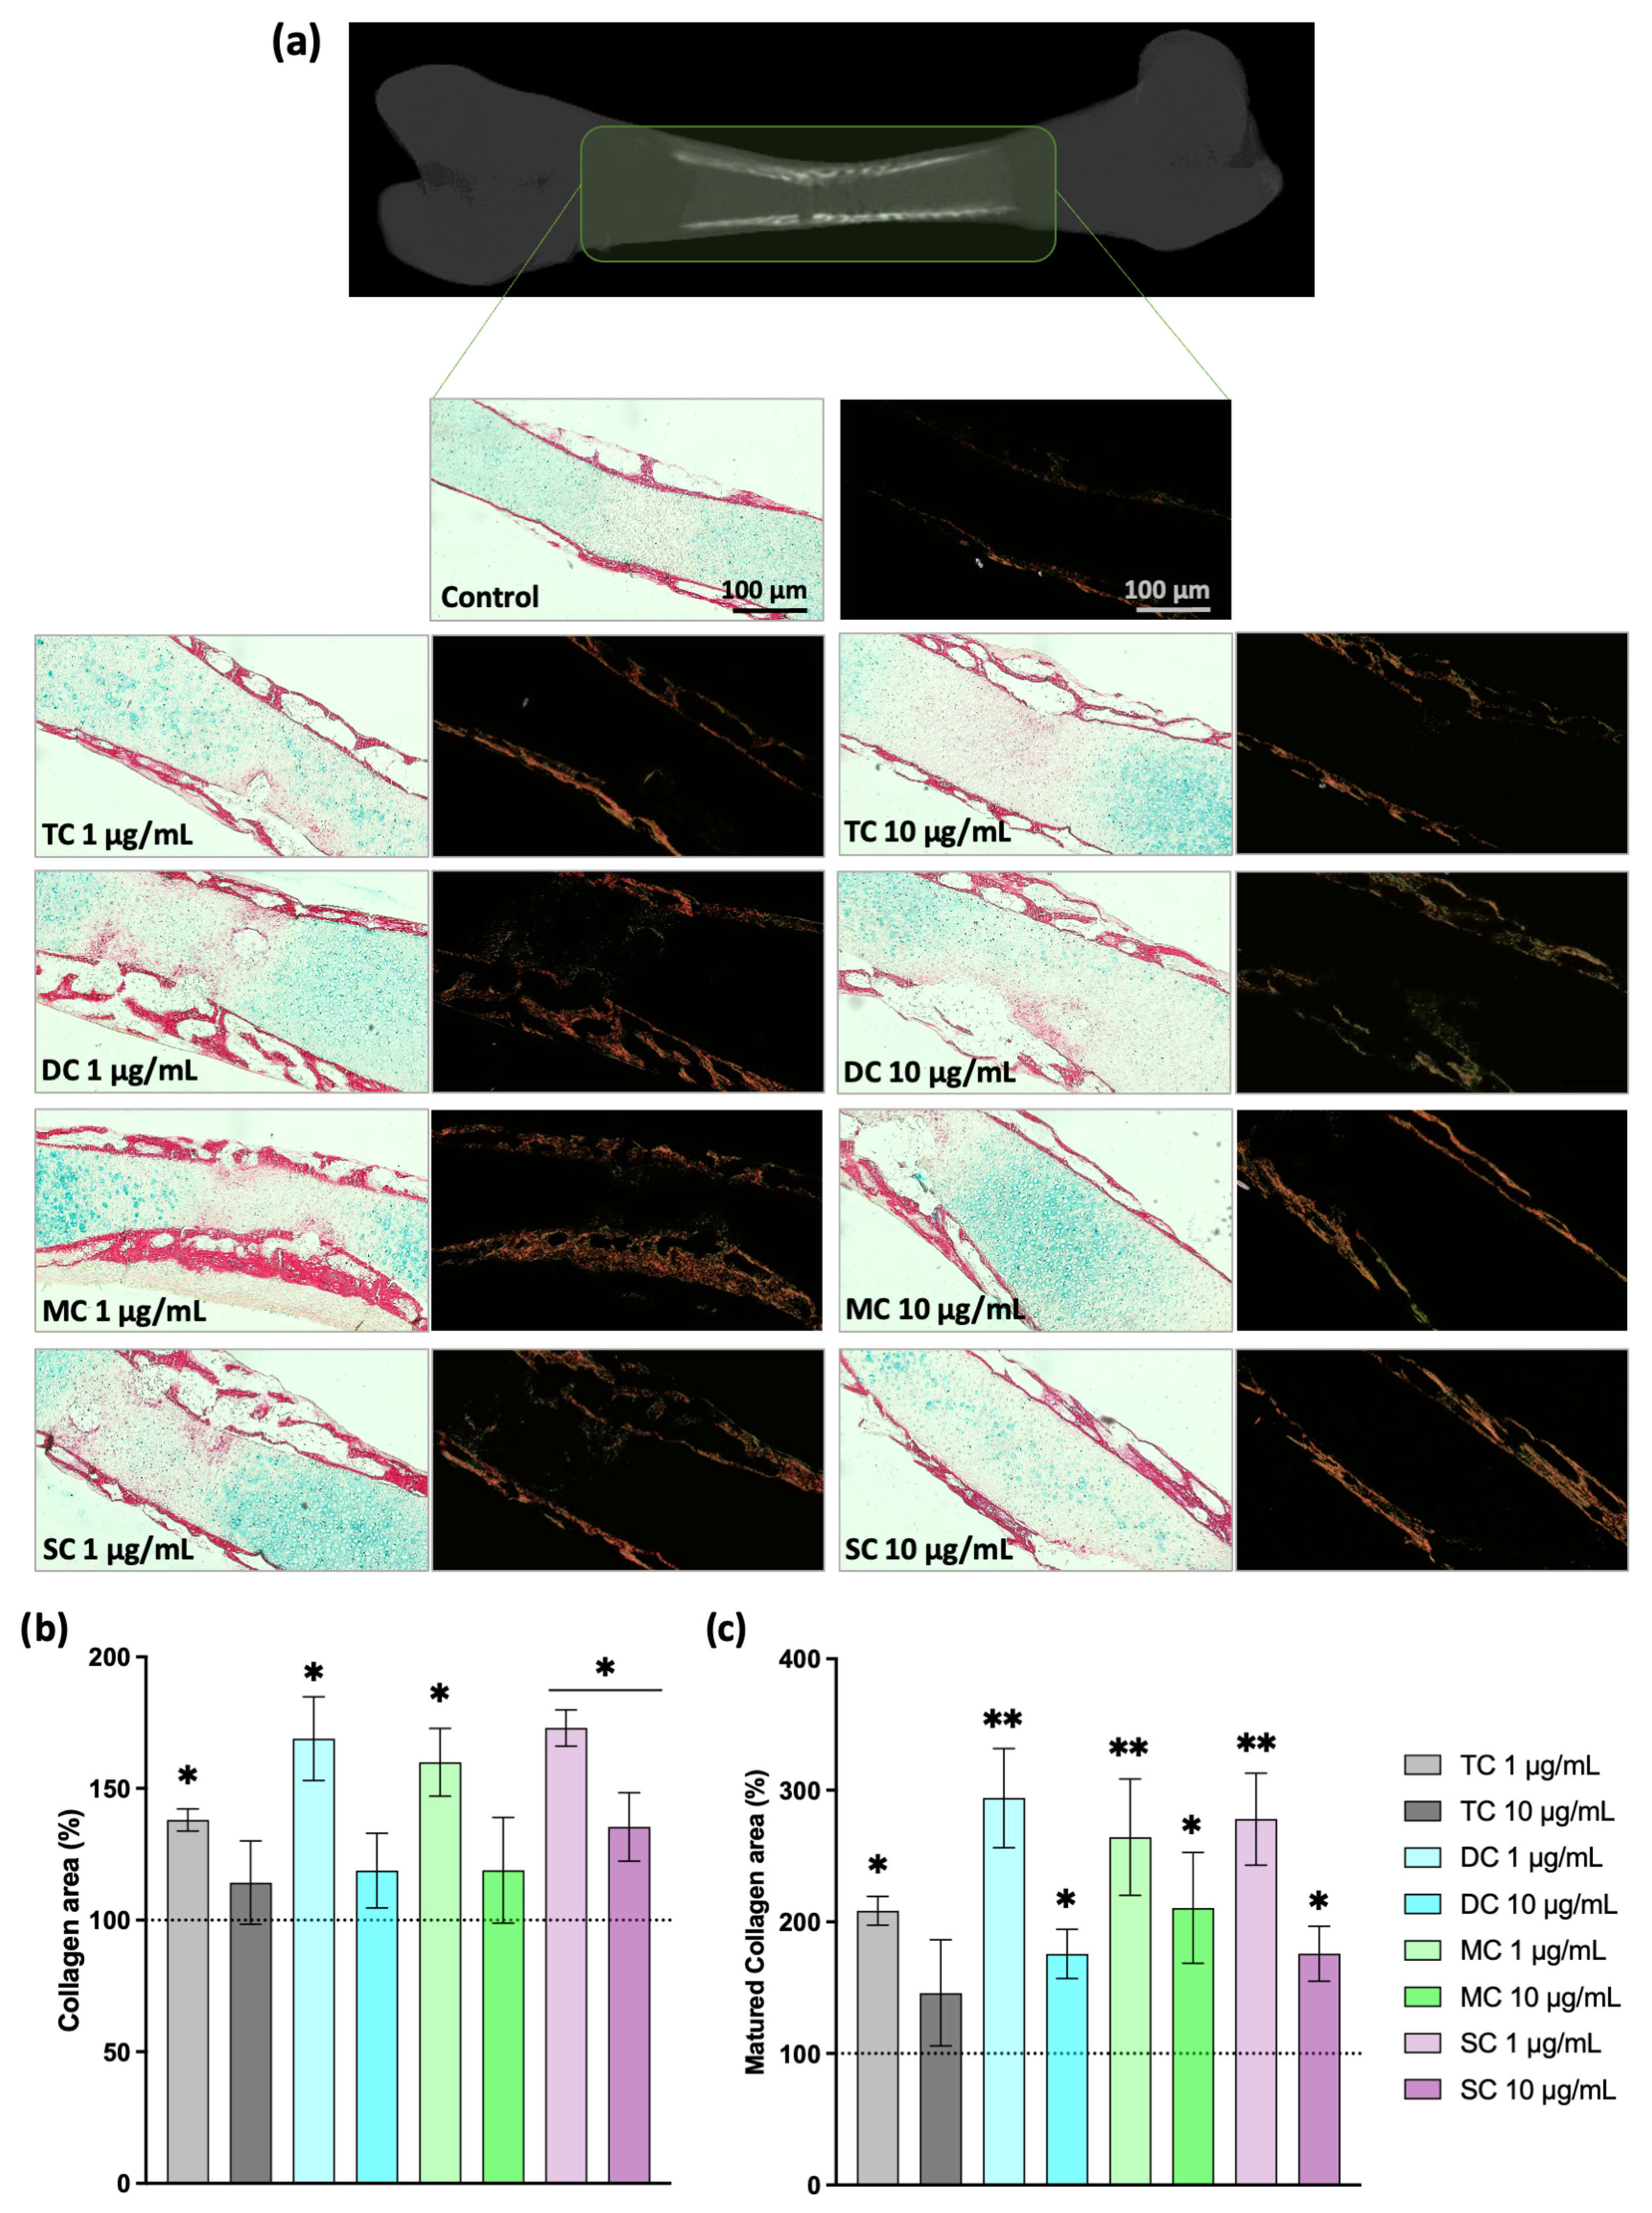
Histochemical staining (Figure 4a) revealed the composition and structural organization of the diaphyseal and metaphyseal regions of the femora. The control group exhibited a continuous collagen-rich outer layer (red) and a central cartilaginous core (blue). Under polarized light, only a dimmed and thin layer of mature collagen with weak birefringence was observed. In contrast, while all tetracycline-exposed groups displayed comparable tissue composition and organization, notable differences were observed, including a thicker, more developed collagen layer, along with evident zones of cellular migration towards the diaphyseal interior. These differences were further highlighted under polarized light, where enhanced birefringence indicated advanced collagen maturation. These findings were supported by the quantitative analysis (Figure 4b,c), which showed significantly increased collagen area in all tetracycline groups, especially in femora treated with MC, DC, and SC groups at 1 µg/mL.
Figure 4.
(a) Representative images of sagittal femoral sections stained with AB/SR under brightfield and polarized illumination. (b,c) Quantitative analysis of collagenous tissue area (%) under both illumination conditions. Under polarized light, mature fibrils appear yellow to red, while less mature fibrils appear green. Results were normalized to the control group, set as 100%, represented by the dashed line. (*) different from the control, p ≤ 0.05. (**) different from the control, p ≤ 0.01, n = 5. For reference, the absolute collagen area values (%) are as follows: Control–5.32; TC 1 µg/mL–7.34; TC 10 µg/mL–6.14; DC 1 µg/mL–8.52; DC 10 µg/mL–6.32; MC 1 µg/mL–8.31; MC 10 µg/mL–6.33; SC 1 µg/mL–8.71; SC 10 µg/mL–7.18. For reference, the absolute matured collagen area values (%) are as follows: Control–1.61; TC 1 µg/mL–3.36; TC 10 µg/mL–2.36; DC 1 µg/mL–4.75; DC 10 µg/mL–3.19; MC 1 µg/mL–4.27; MC 10 µg/mL–3.43; SC 1 µg/mL–4.49; SC 10 µg/mL–3.16.
2.3. Assessment of Gene Expression (qPCR)
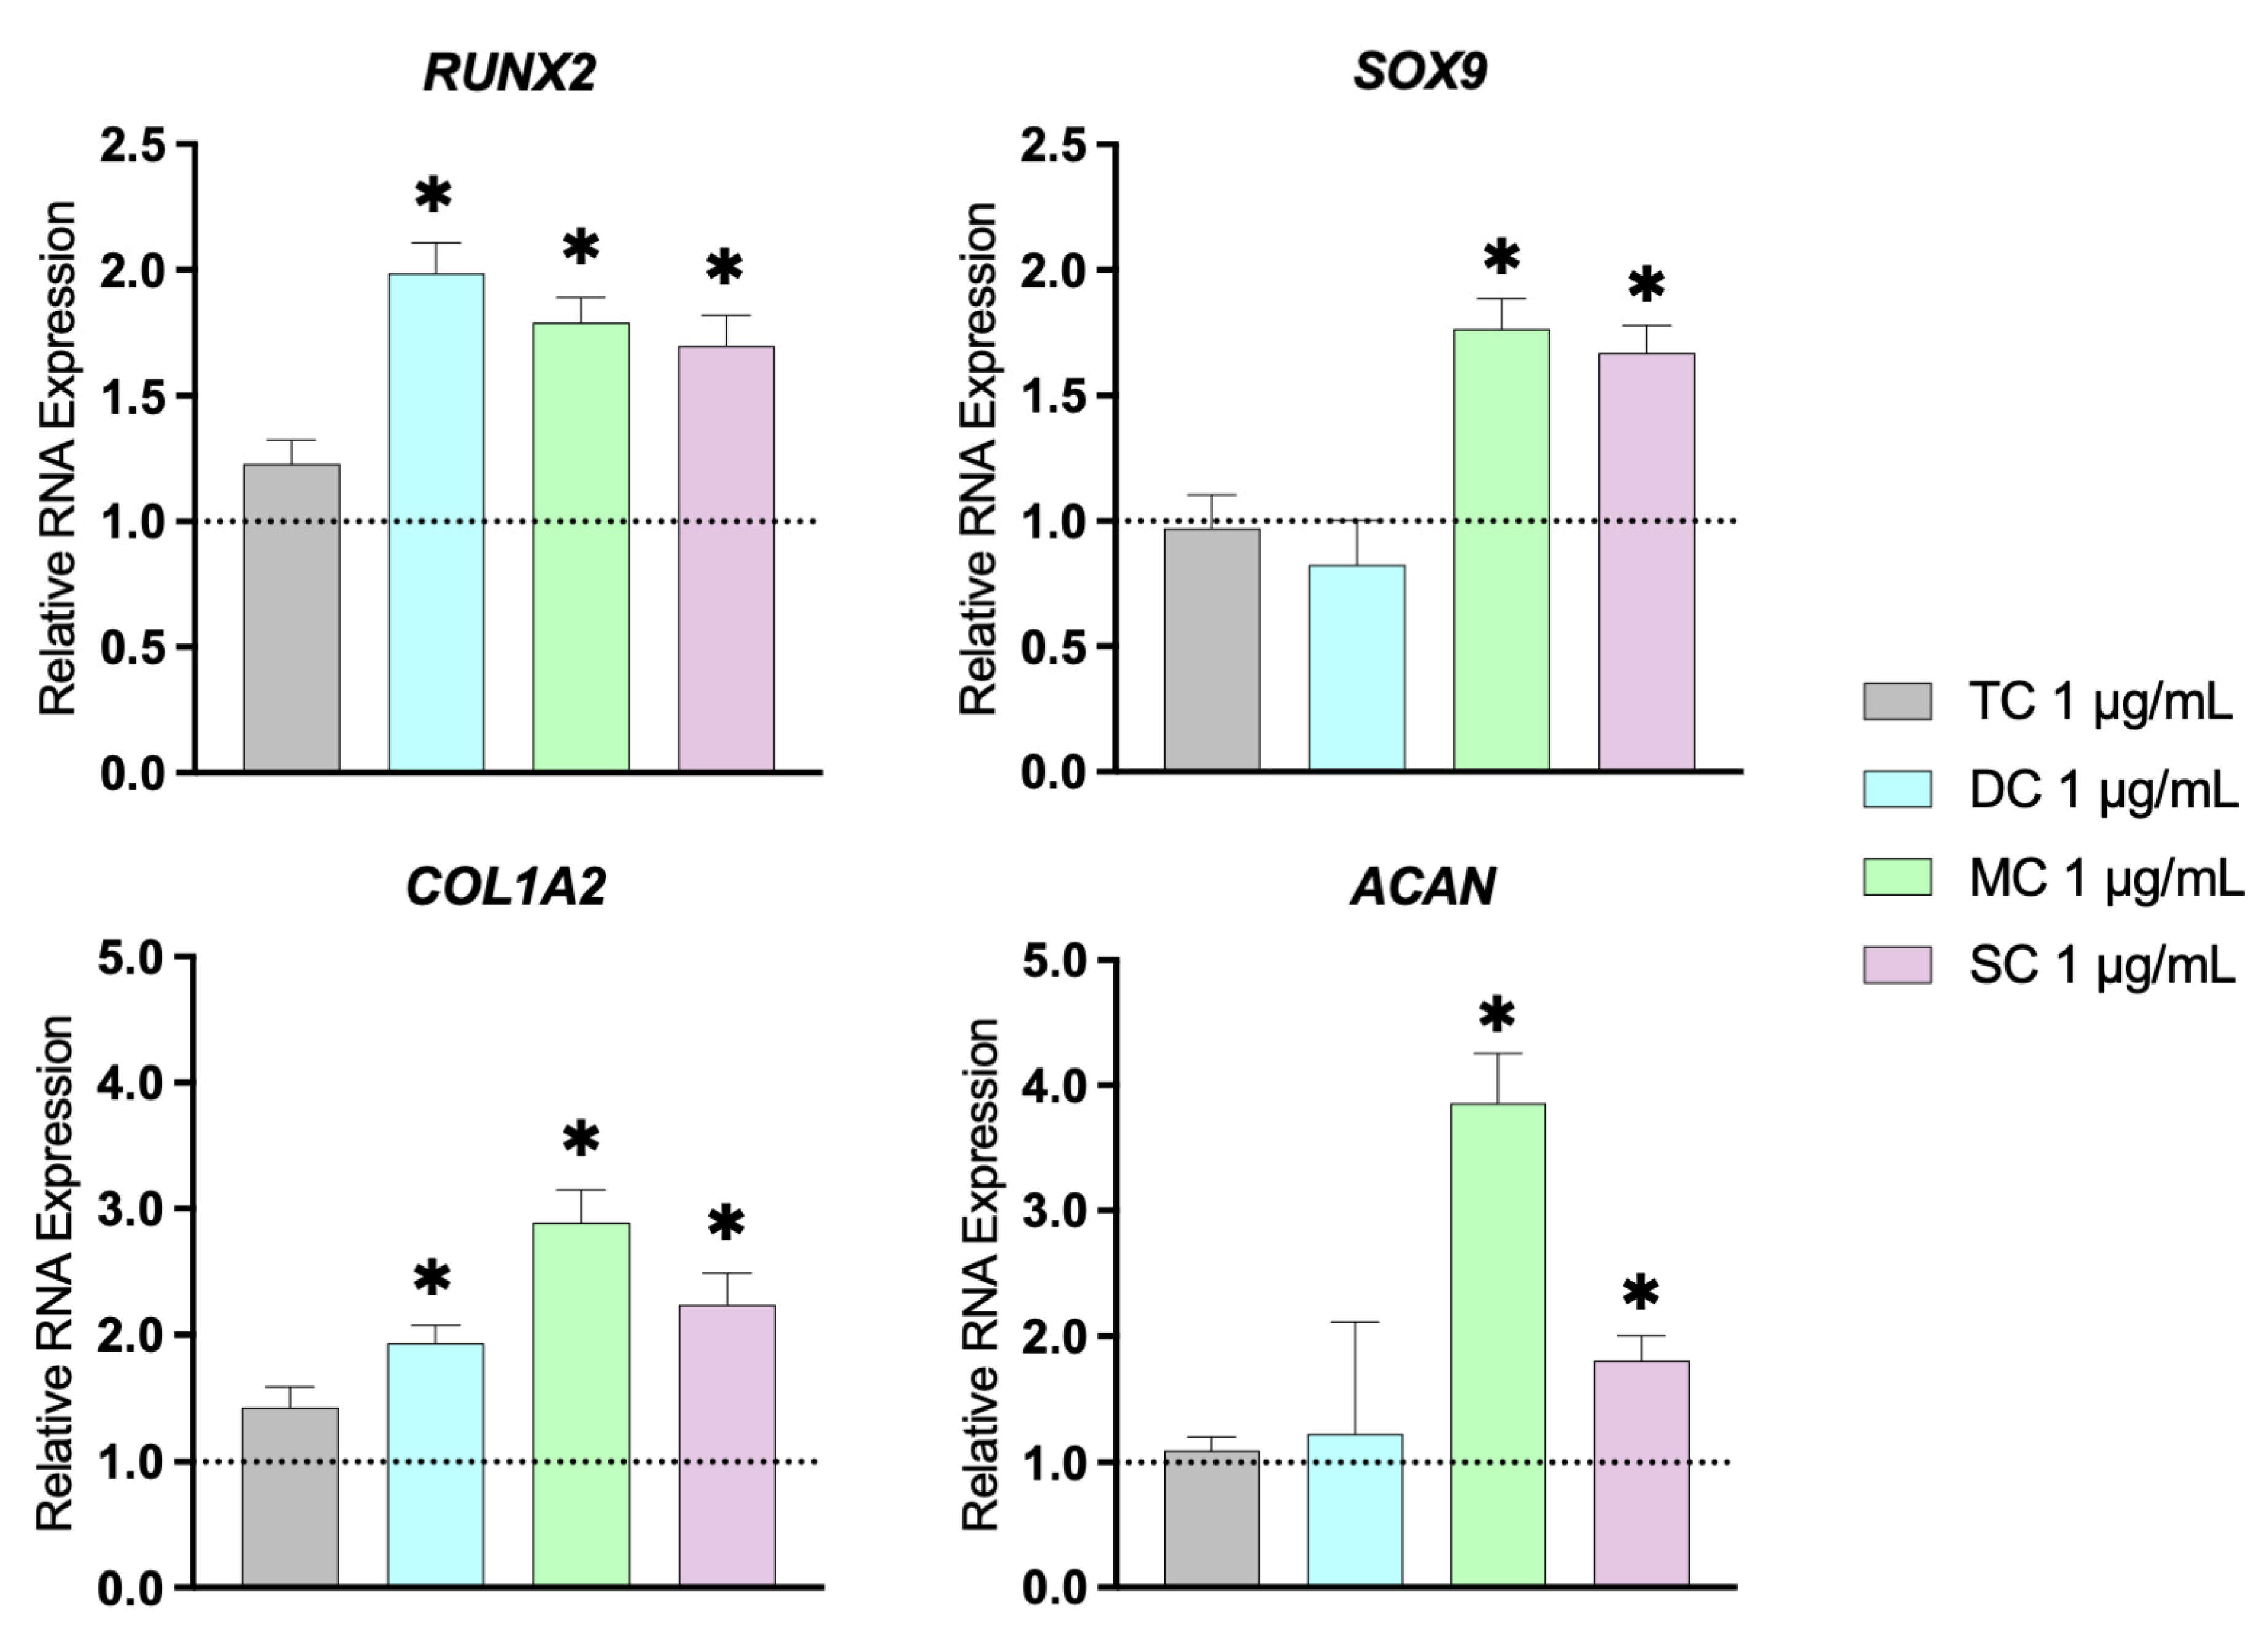
Given that the most pronounced effects on collagen deposition (Figure 4) and mineralization (Figure 3) occurred at 1 µg/mL, gene expression analysis was conducted upon exposure to this concentration. As displayed in Figure 5, DC, MC, and SC significantly upregulated the expression of Runt-related transcription factor 2 (RUNX2) and collagen type I alpha 2 (COL1A2), whereas TC exerted only a minimal effect. For aggrecan (ACAN), MC and SC induced substantial upregulation, whereas TC and DC showed levels comparable to those of the control. Likewise, SRY-box transcription factor 9 (SOX9) expression was upregulated only by MC and SC.
Figure 5.
Relative expression of osteogenic and chondrogenic genes upon culture with tetracyclines at 1 µg/mL, assessed by qPCR. Values were normalized to GAPDH using the 2−ΔΔCt method. The control group was set as 1.0, represented by the dashed line. (*) different from the control, p ≤ 0.05. n = 5.
3. Discussion
The present study provides a direct comparison of four tetracycline derivatives, representing different antibiotic generations, on bone tissue dynamics. This investigation focused on concentrations consistent with those typically achieved through oral administration [6,17], as well as those potentially attainable with local controlled drug-delivery systems [21,22]. To date, most knowledge of tetracycline-mediated bone effects has been derived from in vitro cellular studies, whereas tissue-level evidence remains scarce. In particular, no cross-generation comparative analysis of tetracycline agents at clinically relevant concentrations for bone tissue modulation has been reported. In this context, the obtained results provide new evidence on the concentration-related effects of tetracyclines at the tissue level and extend previous in vitro observations into a more translational organotypic framework.
In vitro cell models, although useful for dissecting cellular mechanisms under controlled conditions, lack the cellular diversity, native extracellular matrix, and spatial organization that define bone tissue [19]. In contrast, ex vivo organotypic models preserve these features, enabling the evaluation of cellular response in their native extracellular environment [18]. Moreover, such models minimize the intricacies inherent to in vivo systems, providing a controlled experimental setting in which biological factors can be assessed separately, without the confounding influence of systemic metabolism or immune responses. This approach improves the translational value of findings while further aligning with the principles of 3Rs in biomedical research [19,23].
Within this framework, as shown in Figure 2, incubation with any of the tested tetracyclines at two concentrations (1 and 10 mg/mL) did not significantly affect femoral growth, morphology, or volume. These morphological parameters can be associated with underlying changes in cell viability and proliferation, which have been extensively evaluated in vitro. Therefore, our findings are in line with the literature, showing a concentration-related influence of tetracyclines on cell proliferation—concentrations below 10 µg/mL generally exert minimal or no effect [16,24,25], whereas higher doses often inhibit cell proliferation [26,27], although exceptions have been reported depending on incubation time and experimental conditions [17,28]. Mechanistically, eukaryotic cells present reduced ribosomal sensitivity to tetracyclines and lack the active transport systems found in bacteria, resulting in significantly lower intracellular drug concentrations [5]. Even so, tetracyclines can cross the eukaryotic cell membrane by passive diffusion [29,30]. Once internalized, they can interact with mitochondria, impairing their function and reducing oxygen consumption, thereby shifting cellular metabolism toward glycolysis [24,31]. Therefore, at sufficiently high concentrations, these combined effects culminate in inhibition of protein synthesis and, consequently, a reduction in proliferation rate. The absence of growth inhibition in our model thus likely reflects that the tested concentrations remained below this cytostatic threshold.
While overall growth remained unaffected, clear differences emerged in osteogenic induction. At 1 µg/mL, all tetracyclines enhanced collagen deposition, collagen maturation, and matrix mineralization (Figure 3 and Figure 4). These effects were associated with the upregulation of key osteogenic genes (Figure 5). Across DC, MC, and SC, a consistent pattern of osteogenic commitment emerged, marked by significant increases in RUNX2 and COL1A2 expression. Moreover, MC and SC concomitantly upregulated SOX9 and ACAN, genes associated with osteochondrogenic commitment and endochondral ossification, respectively [32]. Despite these transcriptional differences in the osteochondrogenic program, no apparent variation in tissue structure or composition was noticed among groups, suggesting that gene-level divergences may reflect early regulatory events but not be fully manifested at the tissue level during the culture period.
Regarding osteogenesis, RUNX2 emerged as a central driver of this response, in line with its well-established role as a master transcription factor in bone formation [33]. Through coordinated genetic and epigenetic mechanisms, RUNX2 orchestrates the transcription of osteogenic genes, directs the differentiation of mesenchymal progenitors into the osteoblastic lineage, and promotes the expression of downstream markers such as alkaline phosphatase (ALP) and extracellular matrix proteins, thereby facilitating early matrix mineralization [33,34]. Consistent with previous studies in murine and human cell culture systems, low doses of DC and MC consistently upregulated RUNX2 and early osteogenic markers [12,16,28,35]. Although SC has been less explored for osteogenic applications, our previous findings confirm that SC at 1 µg/mL significantly upregulated RUNX2 and enhanced ALP activity in BMCs, underscoring its potential beyond dermatological applications [16,36].
The impact on type I collagen was equally notable. As the predominant organic component of the bone extracellular matrix, encoded by the COL1A1 and COL1A2 genes, collagen provides a platform for calcium phosphate deposition, thereby facilitating mineralization [34,37]. Consistent with the upregulation of COL1A2, tetracycline exposure increased collagen deposition, as confirmed by histochemical staining, and promoted fibril maturation and organization (Figure 4). This effect was particularly pronounced at 1 µg/mL, suggesting a concentration window in which tetracyclines enhance matrix quality without disrupting cellular metabolism. Two main mechanisms may underlie these effects. First, tetracyclines can directly stimulate the transcription of COL genes (COL1A1 and COL1A2), thereby enhancing type I collagen biosynthesis [35,38,39]. Mechanistically, this has been linked to the activation of RUNX2-dependent transcriptional programs and modulation of TGF-β/Smad signaling, both of which promote collagen gene expression and osteoblast differentiation [12,16,28,35]. By increasing collagen synthesis at the gene level, tetracyclines expand the extracellular scaffold available for mineral deposition and improve the structural integrity of the developing bone matrix. Second, tetracyclines exert intrinsic anti-collagenase activity, inhibiting the activation of pro-MMPs and neutralizing active MMPs, thereby protecting newly synthesized fibrils from premature enzymatic degradation and favoring their stabilization within the matrix [40,41].
Together, these mechanisms may not only increase the overall collagen content but also create favorable conditions for fibril maturation. Collagen maturation, as reflected by birefringence under polarized light, is a critical step in the mineralization process [18]. Through enzymatic and non-enzymatic cross-linking, collagen fibrils acquire greater stability and tensile strength, which reinforces the extracellular matrix, providing a highly organized template for subsequent mineral deposition [37,42,43]. The improvement in fibril organization observed in tetracycline-exposed femora (Figure 4) suggests that, beyond stimulating synthesis and preventing degradation, these agents actively promote matrix quality. This is particularly relevant because collagen maturation determines the mechanical competence of bone and directly influences its capacity to undergo proper mineralization [42]. Similar outcomes have been reported in vitro, where DC restored total collagen synthesis under pathological conditions [35].
Consistent with the matrix-level changes observed, DC, MC, and SC at 1 µg/mL promoted mineral deposition, as evidenced by a significantly higher bone volume and bone volume fraction (BV/TV) in microtomographic analysis (Figure 3). Nonetheless, at 10 µg/mL, the osteoinductive effect was diminished across all tetracycline agents, resulting in matrix mineralization levels comparable to control. These findings are particularly pertinent to locally delivered therapies, where tetracycline levels often exceed those achieved through systemic administration [17,22]. Accordingly, the design of local-delivery systems must carefully regulate both the total tetracycline load and the release kinetics. This is essential to prevent the buildup of locally high concentrations that may exert detrimental effects on bone cells, while ensuring sustained exposure within the range that supports optimal osteogenic activity.
Such concentration-related effects are consistent with previous in vitro studies, in which bone marrow cells (BMCs) cultured with DC or MC at 1 µg/mL stimulated early mineral deposition, whereas higher concentrations abolished this effect [17,44]. Likewise, TC at 20–25 µg/mL failed to promote osteogenic activity in mesenchymal progenitors, underscoring the limited benefit of higher tetracycline concentrations [25,45]. The inhibition of biomineralization at higher concentrations may occur via distinct mechanisms. By chelating calcium, tetracyclines reduce the extracellular ion availability for cellular uptake [46]. Consequently, cytosolic calcium levels decline, disrupting critical intracellular signaling pathways (e.g., Ca2+/calmodulin-dependent kinases and the calcineurin–NFAT pathway) required for osteogenic differentiation [46]. In addition, adequate cytosolic calcium is critical for the biogenesis and secretion of matrix vesicles, which are enriched in calcium-binding proteins (e.g., annexins) and alkaline phosphatase and that nucleate calcium phosphate crystals [47]. Calcium depletion compromises vesicle formation and mineral crystal initiation, ultimately impairing matrix mineralization [34]. Furthermore, by potentially competing with citrate for binding sites on hydroxyapatite, high tetracycline levels may reduce citrate incorporation into the bone matrix, ultimately affecting the biomineralization process [48,49,50]. By contrast, lower concentrations of tetracyclines appear insufficient to disrupt calcium homeostasis, allowing their pro-osteogenic actions—such as gene upregulation and matrix stabilization—to prevail.
Notably, this enhancement at the lower tested concentration was not uniform across agents. TC showed a markedly weaker osteogenic response, failing to enhance mineralized tissue volume even at 1 µg/mL. This comparatively lower effect may be attributed to two independent factors. TC has a reduced capacity to form neutrally charged complexes with divalent cations under physiological conditions, which can limit its effective cellular interaction and uptake [51]. Additionally, structural differences between TC and the more potent derivatives, MC and SC, may limit its ability to modulate osteogenic signaling pathways [16,35,39]. SC and MC share a common tetracycline scaffold with optimized substituents at the R7 position (Figure 1), which strengthens their bioactivity. TC and DC lack this modification—a key structural feature associated with enhanced osteogenic potential [5,16]. Although DC does not feature the substitution at the R7 position, it presents structural optimizations relative to TC (at R5 and R6 positions) that may partially offset this absence by increasing DC cellular activity and uptake, thereby aligning its performance more closely with MC and SC in the osteogenic assessment.
This study has some limitations. First, only two concentrations within the cytocompatible range were tested, which limits our ability to identify potential deleterious or cytotoxic effects of tetracyclines at the tissue level. Second, although SR staining enables the visualization of collagen fiber orientation and thickness, it does not allow for discerning among collagen types or their quantification, nor does it reveal other relevant components of the bone matrix, including periosteal structures, muscle insertions, or non-collagenous fibers, which would require alternative histochemical or immunohistochemical methods. Consequently, complementary staining techniques (e.g., Mallory’s trichrome, collagen-type-specific immunohistochemistry) would be necessary to achieve a more comprehensive characterization of the bone microenvironment.
Taken together, these observations highlight that subtle structural modifications across tetracycline generations can translate into marked differences in bone responses, underscoring the need for careful agent selection when considering tetracyclines for bone-targeted applications.
4. Materials and Methods
4.1. Preparation of Tetracycline Solutions
Tetracycline hydrochloride (TC, T8032, Sigma-Aldrich), doxycycline hydrochloride (DC, D3447, Sigma-Aldrich, St. Louis, MO, USA), minocycline hydrochloride (MC, M9511, Sigma-Aldrich, St. Louis, MO, USA), and sarecycline hydrochloride (SC, P005672, Adooq Bioscience, Irvine, CA, USA) were dissolved in sterile phosphate-buffered saline (PBS) to obtain stock solutions at 10 µg/mL and 100 µg/mL. All stock solutions were freshly prepared, aliquoted to prevent repeated freeze–thaw cycles, and stored at −20 °C. Both stock and working solutions were protected from light to minimize degradation.
4.2. Organotypic Femur Culture and Characterization Under Tetracycline Exposure
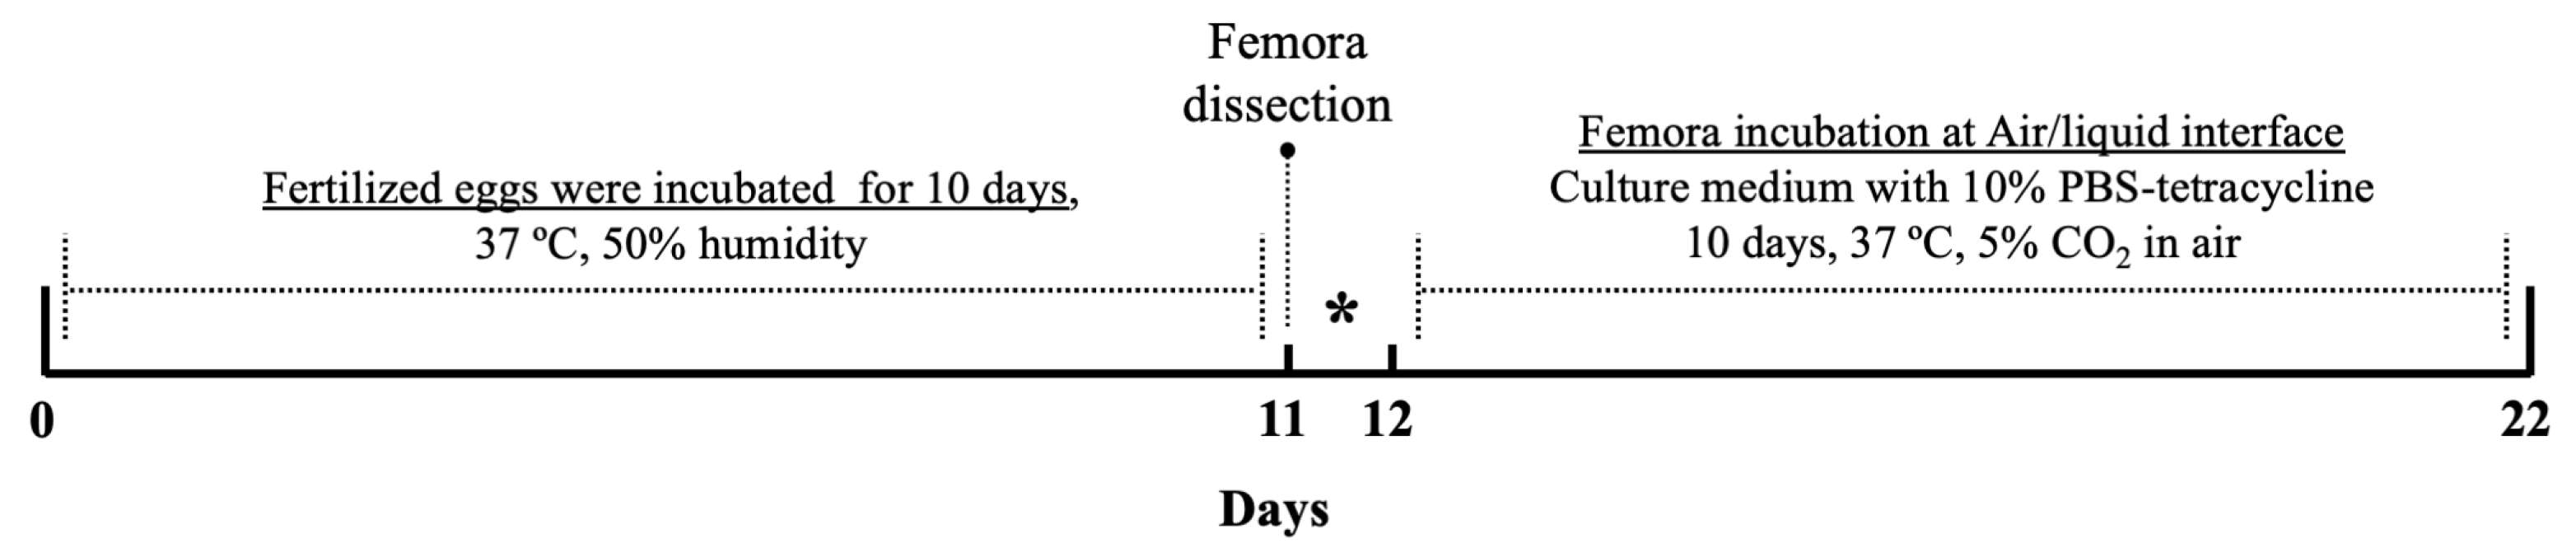
Fertilized chick eggs (Gallus domesticus) were incubated for 11 days in an Octagon 40 ECO rotating egg incubator (Brinsea, Weston-Super-Mare, UK), at 37 °C and 50% humidity. Both femora were dissected from 11-day-old chick embryos and carefully placed into NetwellTM inserts (440 µm pore diameter, Costar 3480, Tewksbury, MA, USA) within six-well plates. Femora were randomly assigned to either the experimental or the control group, and were kept for 24 h in minimum essential medium (α-MEM), containing ascorbic acid (50 μg/mL), penicillin (100 U/mL), streptomycin (100 μg/mL), and amphotericin B (2.5 μg/mL), all from Gibco (Gibco, Waltham, MA, USA), at the air/liquid interface under a humidified atmosphere of 5% CO2 in air, at 37 °C. The medium was then replaced with identical culture medium containing 10% PBS-antibiotic solution, resulting in final drug concentrations of 1 or 10 µg/mL. This concentration range encompasses serum levels typically achieved with conventional oral administration, as well as those potentially attainable via local drug-delivery strategies [6,21,22]. The control group was incubated with medium containing 10% PBS without tetracyclines. Culture media were changed daily. At the end of the 11-day incubation period, femora were washed twice in PBS and either fixed in 4% paraformaldehyde or snap-frozen in liquid nitrogen for subsequent analysis. The experimental workflow is illustrated in Figure 6. Bone samples were subjected to dimensional measurements, microcomputed tomography, histological evaluation, and gene expression profiling. Since the use of avian embryos during the first two-thirds of development for research purposes is not covered by European (Directive 2010/63/EU) or National (Decreto-Lei n.° 113/2013) legislation, no specific regulatory approval was required to conduct the experimental procedures.
Figure 6.
Schematic representation of the experimental design, including the incubation timeline and culture conditions. * 24 h femora incubation at air/liquid interface with tetracycline-free medium. Culture medium: minimum essential medium (α-MEM), containing ascorbic acid (50 μg/mL), penicillin (100 U/mL), streptomycin (100 μg/mL), and amphotericin B (2.5 μg/mL). Culture media were changed daily. At day 22, the assay was terminated—Femora were harvested for fixation in 4% paraformaldehyde or snap-freezing in liquid nitrogen.
4.2.1. Whole-Bone Dimensional Analysis
Femora were photographed at the beginning and end of the culture period, and longitudinal bone growth was quantified by measuring bone length using ImageJ software (v.1.53k).
4.2.2. Bone Morphometric Analysis by Micro-Computed Tomography (µCT) and Histomorphometric Assessment
Fixed femora were scanned at 40 kV, 100 μA, 800 ms, with an isotropic resolution of 4.5 μm, using a Skyscan 1276 System (Bruker, Kontich, Belgium). Three-dimensional (3D) reconstructions were obtained from projection images using NRecon software (Bruker, v.1.7.4.2). Delimitation of the volume of interest (VOI) as well as morphological analysis were conducted using CTAnalyser software (Bruker, v.1.19.3.1), where whole femora, including diaphyseal, metaphyseal, and epiphyseal regions, were quantitatively analyzed for bone volume (BV), tissue volume (TV), and bone mineral density (BMD). Representative images of reconstructed femora were obtained using CTVox software (Bruker, v. 2.3.2.1). The assay was conducted in quintuplicate.
4.2.3. Histological Evaluation
Histochemical staining was performed on 5 µm-thick sections of whole femora embedded in paraffin blocks. Sections were stained with Alcian blue/Sirius red (AB/SR), marking glycosaminoglycans and the collagenous matrix, respectively. Images were captured using a Zeiss Axiolab 5 microscope coupled with an Axiocam 5 Color Camera (Zeiss, Oberkochen, Germany). Moreover, the collagen area (%) was calculated using ImageJ software (v.1.53k) using the Otsu algorithm to set the threshold. Further, AB/SR-stained sections were examined under polarized light to assess collagen fiber birefringence, enabling quantitative analysis [18]. The assay was conducted in quintuplicate.
4.2.4. Assessment of Gene Expression by Quantitative PCR (qPCR)
Frozen femora were lysed in TRIzol (Invitrogen, San Diego, CA, USA) reagent for total RNA extraction following the manufacturer’s protocol. RNA quality and concentration were assessed using a Gen5 Take3 module and a microplate reader (Synergy HT, both from Biotek) by absorbance reading (260/280 nm). RNA samples that met acceptable purity (1.9–2.1 ratio) were converted to cDNA using an NZY Kit, followed by incubation with RNase (both from NZYTech, Lisbon, Portugal) at 37 °C for 20 min. Real-time qPCR was performed using a CFX384 PCR system (Bio-Rad, Hercules, CA, USA) following the Bio-Rad cycling protocol. The converted cDNAs were added to a mixture of iTaq Universal SYBR green Supermix, DEPC water, and the selected primers (Table 1), all from Bio-Rad. The primer panel included transcription factors and genes encoding extracellular matrix proteins associated with osteogenesis (RUNX2, COL1A2) and chondrogenesis (SOX9, ACAN). After the reaction, values from samples that met the quality check (i.e., amplification efficiency (90–100%) and linearity R2 > 0.97) were selected. The relative quantification of each target gene was normalized to GAPDH levels and calculated via the 2−ΔΔCt method. Five independent experiments were performed.
Table 1.
Primers used in the QPCR reaction, identified by their unique assay ID from the manufacturer.
4.3. Statistical Analysis
Each femur was considered an independent biological replicate as they were each randomly assigned to the experimental or control groups. Data were analyzed using SPSS software (v.28, IBM). Data normality was checked using the Shapiro–Wilk test. Parametric datasets were analyzed by one-way ANOVA, followed by Tukey’s multiple comparisons test. For nonparametric datasets, the Kruskal–Wallis test with Dunn’s post hoc comparisons was performed. Significance was set at p ≤ 0.05. Results were presented as mean ± standard deviation (SD). Experimental groups were compared with the control group.
5. Conclusions
Setting on an advanced organotypic model, the present study demonstrates that the osteogenic effects of four clinically relevant tetracycline agents—spanning all three generations—are both agent– and concentration-related. At 1 µg/mL, all compounds enhanced osteogenesis, as evidenced by increased expression of osteogenic markers, collagen deposition and maturation, and tissue mineralization, although TC exhibited a comparatively diminished effect. At 10 µg/mL, the osteogenic stimulation was markedly attenuated, yet without negatively impacting bone growth or volume, supporting that low concentrations of DC, MC, or SC hold greater potential for bone regenerative applications.
Despite comparable osteogenic performance, DC, MC, and SC exhibited distinct osteochondrogenic gene expression profiles, suggesting that they may differentially regulate the molecular balance between bone and cartilage differentiation. Further investigation is warranted to elucidate their role in osteochondrogenesis and the molecular mechanisms underlying these divergences. Given the pivotal role of coordinated bone–cartilage dynamics in conditions such as osteoarthritis and osteochondral defects, elucidating how individual tetracycline derivatives modulate interfacial tissue behavior is essential to advancing their targeted use in regenerative medicine.
Author Contributions
Conceptualization, C.S. and P.S.G.; Data curation, V.M.; Formal analysis, A.F.B., C.S. and V.M.; Funding acquisition, A.F.B., C.S., M.H.F. and P.S.G.; Investigation, A.F.B., C.S. and V.M.; Methodology, M.H.F., P.S.G. and V.M.; Project administration, P.S.G.; Supervision, A.F.B., C.S. and P.S.G.; Validation, M.H.F. and P.S.G.; Visualization, V.M.; Writing—original draft, V.M.; Writing—review & editing, A.F.B., C.S., M.H.F., and P.S.G. All authors have read and agreed to the published version of the manuscript.
Funding
This work received financial support from national funds (FCT/MCTES, Fundação para a Ciência e Tecnologia and Ministério da Ciência, Tecnologia e Ensino Superior, Portugal) through project 2022.06464.PTDC (https://doi.org/10.54499/2022.06464.PTDC). Also, A. Bettencourt (from iMed.ULisboa) thanks the Fundação para a Ciência e Tecnologia (FCT), Portugal for the financial support: projects UID 04138 Instituto de Investigação do Medicamento (iMed.ULisboa). C. Santos acknowledges funding from the Fundação para a Ciência e a Tecnologia (FCT) through the Research Unit Centro de Química Estrutural (CQE) projects UIDB/00100/2020 and UIDP/00100/2020, as well as the Institute of Molecular Sciences (IMS) project LA/P/0056/2020.
Institutional Review Board Statement
The use of avian embryos during the first two-thirds of development for research purposes is not covered by European (Directive 2010/63/EU) or National (Decreto-Lei n.° 113/2013) legislation, no specific regulatory approval was required to conduct the experimental procedures.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data that support the findings of this study are available from the corresponding authors upon request.
Acknowledgments
The authors acknowledge the support of the i3S Scientific Platform Bioimaging, a member of the PPBI (PPBI-POCI-01-0145-FEDER-022122), as well as HEMS—Histology and Electron Microscopy Department.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Bunick, C.G.; Keri, J.; Tanaka, S.K.; Furey, N.; Damiani, G.; Johnson, J.L.; Grada, A. Antibacterial Mechanisms and Efficacy of Sarecycline in Animal Models of Infection and Inflammation. Antibiotics 2021, 10, 439. [Google Scholar] [CrossRef] [Scilit]
- Ramachanderan, R.; Schaefer, B. Tetracycline Antibiotics. ChemTexts 2021, 7, 18. [Google Scholar] [CrossRef] [Scilit]
- LaPlante, K.L.; Dhand, A.; Wright, K.; Lauterio, M. Re-Establishing the Utility of Tetracycline-Class Antibiotics for Current Challenges with Antibiotic Resistance. Ann. Med. 2022, 54, 1686–1700. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martin, V.; Francisca Bettencourt, A.; Santos, C.; Sousa Gomes, P. Reviewing Particulate Delivery Systems Loaded with Repurposed Tetracyclines—From Micro to Nanoparticles. Int. J. Pharm. 2024, 649, 123642. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rusu, A.; Buta, E.L. The Development of Third-Generation Tetracycline Antibiotics and New Perspectives. Pharmaceutics 2021, 13, 2085. [Google Scholar] [CrossRef] [Scilit]
- Warner, A.J.; Hathaway-Schrader, J.D.; Lubker, R.; Davies, C.; Novince, C.M. Tetracyclines and Bone: Unclear Actions with Potentially Lasting Effects. Bone 2022, 159, 116377. [Google Scholar] [CrossRef] [Scilit]
- Sauer, A.; Putensen, C.; Bode, C. Immunomodulation by Tetracyclines in the Critically Ill: An Emerging Treatment Option? Crit. Care 2022, 26, 74. [Google Scholar] [CrossRef] [Scilit]
- Garrido-Mesa, J.; Adams, K.; Galvez, J.; Garrido-Mesa, N. Repurposing Tetracyclines for Acute Respiratory Distress Syndrome (ARDS) and Severe COVID-19: A Critical Discussion of Recent Publications. Expert Opin. Investig. Drugs 2022, 31, 475–482. [Google Scholar] [CrossRef] [Scilit]
- Dalhoff, A. Selective Toxicity of Antibacterial Agents—Still a Valid Concept or Do We Miss Chances and Ignore Risks? Infection 2021, 49, 29–56. [Google Scholar] [CrossRef] [Scilit]
- Arslan, M.S.; Öztürk, S.; Kök, R.R.; Beşoluk, K.; Dayan, M.O. Determination of Embryotoxic Dose Limit of Doxycycline and Its Effects on Some Long Bones by In Ovo Model. Anat. Histol. Embryol. 2025, 54, e70030. [Google Scholar] [CrossRef] [Scilit]
- Hadad, H.; de Jesus, L.K.; Pereira-Silva, M.; Oliveira, M.E.d.F.S.; Monteiro, N.G.; Poli, P.P.; Maiorana, C.; Okamoto, R.; Guastaldi, F.P.S.; de Almeida, J.M.; et al. The Role of a Local Application of 10% Doxycycline Gel in the Prevention of Medication-Related Osteonecrosis of the Jaw in Rats. Clin. Oral Investig. 2025, 29, 205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toledano-Osorio, M.; de Luna-Bertos, E.; Toledano, M.; Manzano-Moreno, F.J.; Costela-Ruiz, V.; Ruiz, C.; Gil, J.; Osorio, R. Dexamethasone and Doxycycline Functionalized Nanoparticles Enhance Osteogenic Properties of Titanium Surfaces. Dent. Mater. 2023, 39, 616–623. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohammad, C.A.; Ali, K.M.; Al-rawi, R.A.; Gul, S.S. Effects of Curcumin and Tetracycline Gel on Experimental Induced Periodontitis as an Anti-Inflammatory, Osteogenesis Promoter and Enhanced Bone Density through Altered Iron Levels: Histopathological Study. Antibiotics 2022, 11, 521. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, X.; Zhang, P.; Zhang, C.; An, B.; Zhu, Z. Tetracyclines Inhibit Rat Osteoclast Formation and Activity In Vitro and Affect Bone Turnover in Young Rats In Vivo. Calcif. Tissue Int. 2010, 86, 163–171. [Google Scholar] [CrossRef] [Scilit]
- Bettany, J.T.; Peet, N.M.; Wolowacz, R.G.; Skerry, T.M.; Grabowski, P.S. Tetracyclines Induce Apoptosis in Osteoclasts. Bone 2000, 27, 75–80. [Google Scholar] [CrossRef] [Scilit]
- Martin, V.; Bettencourt, A.F.; Santos, C.; Fernandes, M.H.; Gomes, P.S. Unveiling the Osteogenic Potential of Tetracyclines: A Comparative Study in Human Mesenchymal Stem Cells. Cells 2023, 12, 2244. [Google Scholar] [CrossRef] [Scilit]
- Gomes, P.S.; Fernandes, M.H. Effect of Therapeutic Levels of Doxycycline and Minocycline in the Proliferation and Differentiation of Human Bone Marrow Osteoblastic Cells. Arch. Oral Biol. 2007, 52, 251–259. [Google Scholar] [CrossRef] [Scilit]
- Furtado, G.S.; Martin, V.; Araújo, R.; Gomes, P.S.; Lago, A.D.N. Osteoinductive Activity of Photobiomodulation in an Organotypic Bone Model. Photodiagnosis Photodyn. Ther. 2024, 45, 103936. [Google Scholar] [CrossRef] [Scilit]
- Rashidi, H.; Cox, H.C.; Qutachi, O.; Moulding, D.; White, L.J.; Smith, E.L.; Kanczler, J.M.; Rojo, L.; Rotherham, M.; Henstock, J.R.; et al. Localized Growth Factor Delivery from Microparticles Modulates Osteogenic and Chondrogenic Gene Expression in a Growth Factor-Dependent Manner in an Ex Vivo Chick Embryonic Bone Model. Acta Biomater. 2025, 204, 558–567. [Google Scholar] [CrossRef] [Scilit]
- Smith, E.L.; Kanczler, J.M.; Roberts, C.A.; Oreffo, R.O.C. Developmental Cues for Bone Formation from Parathyroid Hormone and Parathyroid Hormone-Related Protein in an Ex Vivo Organotypic Culture System of Embryonic Chick Femora. Tissue Eng. Part C Methods 2012, 18, 984–994. [Google Scholar] [CrossRef] [Scilit]
- Nichol, T.; Smith, T.J.; Townsend, R.; Stockley, I.; Akid, R. Analysis of Linezolid and Tigecycline as Candidates for Local Prophylaxis via Antibiotic-Loaded Bone Cement. J. Antimicrob. Chemother. 2017, 72, 410–416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gao, H.; Ge, K.; Xu, Y.; Wang, Y.; Lu, M.; Wei, Y.; Zhu, Q.; Han, X.; Huang, Q.; Cao, Z. Controlled Release of Minocycline in Hydroxyapatite/Chitosan Composite for Periodontal Bone Defect Repair. Dent. Mater. J. 2022, 41, 2021–2217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cramer, E.E.A.; Ito, K.; Hofmann, S. Ex Vivo Bone Models and Their Potential in Preclinical Evaluation. Curr. Osteoporos. Rep. 2021, 19, 75–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Okić Đorđević, I.; Kukolj, T.; Živanović, M.; Momčilović, S.; Obradović, H.; Petrović, A.; Mojsilović, S.; Trivanović, D.; Jauković, A. The Role of Doxycycline and IL-17 in Regenerative Potential of Periodontal Ligament Stem Cells: Implications in Periodontitis. Biomolecules 2023, 13, 1437. [Google Scholar] [CrossRef] [Scilit]
- Macri-Pellizzeri, L.; De Melo, N.; Ahmed, I.; Grant, D.; Scammell, B.; Sottile, V. Live Quantitative Monitoring of Mineral Deposition in Stem Cells Using Tetracycline Hydrochloride. Tissue Eng. Part C Methods 2018, 24, 171–178. [Google Scholar] [CrossRef] [Scilit]
- Almazin, S.M.; Dziak, R.; Andreana, S.; Ciancio, S.G. The Effect of Doxycycline Hyclate, Chlorhexidine Gluconate, and Minocycline Hydrochloride on Osteoblastic Proliferation and Differentiation In Vitro. J. Periodontol. 2009, 80, 999–1005. [Google Scholar] [CrossRef] [Scilit]
- Park, J.B. Effects of Doxycycline, Minocycline, and Tetracycline on Cell Proliferation, Differentiation, and Protein Expression in Osteoprecursor Cells. J. Craniofacial Surg. 2011, 22, 1839–1842. [Google Scholar] [CrossRef] [Scilit]
- El-Habashy, S.; Eltaher, H.; Gaballah, A.; Mehanna, R.; El-Kamel, A.H. Biomaterial-Based Nanocomposite for Osteogenic Repurposing of Doxycycline. Int. J. Nanomed. 2021, 16, 1103–1126. [Google Scholar] [CrossRef] [Scilit]
- Yang, Q.; Nakkula, R.J.; Walters, J.D. Accumulation of Ciprofloxacin and Minocycline by Cultured Human Gingival Fibroblasts. J. Dent. Res. 2002, 81, 836–840. [Google Scholar] [CrossRef] [Scilit]
- Berens, C.; Hillen, W. Gene Regulation by Tetracyclines. Eur. J. Biochem. 2003, 270, 3109–3121. [Google Scholar] [CrossRef] [Scilit]
- Chatzispyrou, I.A.; Held, N.M.; Mouchiroud, L.; Auwerx, J.; Houtkooper, R.H. Tetracycline Antibiotics Impair Mitochondrial Function and Its Experimental Use Confounds Research. Cancer Res. 2015, 75, 4446–4449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, X.; Tian, S.; Fan, L.; Niu, R.; Yan, M.; Chen, S.; Zheng, M.; Zhang, S. Integrated Regulation of Chondrogenic Differentiation in Mesenchymal Stem Cells and Differentiation of Cancer Cells. Cancer Cell Int. 2022, 22, 169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komori, T. Whole Aspect of Runx2 Functions in Skeletal Development. Int. J. Mol. Sci. 2022, 23, 5776. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Margiotta, A. Coupling of Intracellular Calcium Homeostasis and Formation and Secretion of Matrix Vesicles: Their Role in the Mechanism of Biomineralization. Cells 2025, 14, 733. [Google Scholar] [CrossRef] [Scilit]
- Gomes, P.S.; Resende, M.; Fernandes, M.H. Doxycycline Restores the Impaired Osteogenic Commitment of Diabetic-Derived Bone Marrow Mesenchymal Stromal Cells by Increasing the Canonical WNT Signaling. Mol. Cell. Endocrinol. 2020, 518, 110975. [Google Scholar] [CrossRef] [Scilit]
- Martin, V.; Grenho, L.; Fernandes, M.H.; Gomes, P.S. Repurposing Sarecycline for Osteoinductive Therapies: An in Vitro and Ex Vivo Assessment. J. Bone Miner. Metab. 2023, 41, 431–442. [Google Scholar] [CrossRef] [Scilit]
- Landis, W.J.; Jacquet, R. Association of Calcium and Phosphate Ions with Collagen in the Mineralization of Vertebrate Tissues. Calcif. Tissue Int. 2013, 93, 329–337. [Google Scholar] [CrossRef] [Scilit]
- Cardoso, S.; Martin, V.; Pereira, J.C.; David, A.B.; Araújo, R.; Gonçalves, L.; Landin, M.; Gomes, P.; Ferraz, M.P.; Ribeiro, I.A.C.; et al. 3D-Printed Chitosan-Starch Mesh Filled with Minocycline-Alginate Hydrogel for Dual Anti-Staphylococcus Aureus and Osteogenic Effects. Carbohydr. Polym. 2025, 370, 124311. [Google Scholar] [CrossRef] [Scilit]
- Gomes, K.D.N.; Alves, A.P.N.N.; Dutra, P.G.P.; De Barros Viana, G.S. Doxycycline Induces Bone Repair and Changes in Wnt Signalling. Int. J. Oral Sci. 2017, 9, 158–166. [Google Scholar] [CrossRef] [Scilit]
- Tharappel, J.C.; Harris, J.W.; Totten, C.; Zwischenberger, B.A.; Roth, J.S. Doxycycline Alters Collagen Composition Following Ventral Hernia Repair. Surg. Endosc. 2017, 31, 1659–1666. [Google Scholar] [CrossRef] [Scilit]
- Orth, M.W.; Chlebek, K.A.; Cole, A.A.; Schmid, T.M. Tetracycline Derivatives Inhibit Cartilage Degradation in Cultured Embryonic Chick Tibiae. Res. Vet. Sci. 1997, 63, 11–14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Viguet-Carrin, S.; Garnero, P.; Delmas, P.D. The Role of Collagen in Bone Strength. Osteoporos. Int. 2006, 17, 319–336. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Altoé, L.S.; Alves, R.S.; Miranda, L.L.; Sarandy, M.M.; Bastos, D.S.S.; Gonçalves-Santos, E.; Novaes, R.D.; Gonçalves, R.V. Doxycycline Hyclate Modulates Antioxidant Defenses, Matrix Metalloproteinases, and COX-2 Activity Accelerating Skin Wound Healing by Secondary Intention in Rats. Oxidative Med. Cell. Longev. 2021, 2021, 4681041. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gomes, P.S.; Santos, J.D.; Fernandes, M.H. Cell-Induced Response by Tetracyclines on Human Bone Marrow Colonized Hydroxyapatite and Bonelike®. Acta Biomater. 2008, 4, 630–637. [Google Scholar] [CrossRef] [Scilit]
- Wang, W.; Sun, J.; Aarabi, G.; Peters, U.; Fischer, F.; Klatt, J.; Gosau, M.; Smeets, R.; Beikler, T. Effect of Tetracycline Hydrochloride Application on Dental Pulp Stem Cell Metabolism–Booster or Obstacle for Tissue Engineering? Front. Pharmacol. 2023, 14, 1277075. [Google Scholar] [CrossRef] [Scilit]
- Bevelander, G.; Nakahara, H.; Rolle, G.K. The Effect of Tetracycline on the Development of the Skeletal System of the Chick Embryo. Dev. Biol. 1960, 2, 298–312. [Google Scholar] [CrossRef] [Scilit]
- Acharya, T.K.; Pal, S.; Ghosh, A.; Kumar, S.; Kumar, S.; Chattopadhyay, N.; Goswami, C. TRPV4 Regulates Osteoblast Differentiation and Mitochondrial Function That Are Relevant for Channelopathy. Front. Cell Dev. Biol. 2023, 11, 1066788. [Google Scholar] [CrossRef] [Scilit]
- Ibsen, K.H.; Urist, M.R.; Uyeno, S.; Sanders, R.L. Competition between Oxytetracycline and Citrate for Binding Sites on Hydroxyapatite Crystals. Calcif. Tissue Res. 1967, 1, 243–245. [Google Scholar] [CrossRef] [Scilit]
- Costello, L.C.; Chellaiah, M.; Zou, J.; Franklin, R.B.; Reynolds, M.A. The Status of Citrate in the Hydroxyapatite/Collagen Complex of Bone; and Its Role in Bone Formation. J. Regen. Med. Tissue Eng. 2014, 3, 4. [Google Scholar] [CrossRef] [Scilit]
- Dirckx, N.; Zhang, Q.; Chu, E.Y.; Tower, R.J.; Li, Z.; Guo, S.; Yuan, S.; Khare, P.A.; Zhang, C.; Verardo, A.; et al. A Specialized Metabolic Pathway Partitions Citrate in Hydroxyapatite to Impact Mineralization of Bones and Teeth. Proc. Natl. Acad. Sci. USA 2022, 119, e2212178119. [Google Scholar] [CrossRef] [Scilit]
- Lambs, L.; Brion, M.; Berthon, G. Metal Ion-Tetracycline Interactions in Biological Fluids. Part 3. Formation of Mixed-Metal Ternary Complexes of Tetracycline, Oxytetracycline, Doxycycline and Minocycline with Calcium and Magnesium, and Their Involvement in the Bioavailability of These Antibiotics in Blood Plasma. Agents Actions 1984, 14, 743–750. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.