Skip to Content
  • 37 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Trauma Care

Trauma Care is an international, peer-reviewed, open access journal on traumatic injury and psychological trauma published quarterly online by MDPI. 
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 37 days after submission; acceptance to publication is undertaken in 2.9 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.
  • Companion journal: Healthcare.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (171)

  • Review
  • Open Access

Malpractice-Related Stress Among Physicians in Emergency and Acute Care: A Scoping Review

  • Miriam Ottaviani,
  • Federica Spadazzi and
  • Raffaele La Russa
  • + 4 authors

Introduction: Medical malpractice claims and litigation represent potentially relevant occupational stressors for physicians, particularly in high-intensity clinical environments such as emergency medicine and acute care. Epidemiological evidence indicates that malpractice litigation is highly prevalent among physicians. Studies have estimated that by the age of 65 years, approximately 75% of physicians in low-risk specialties have faced at least one malpractice claim, whereas the percentage rises to approximately 99% among physicians in high-risk specialties. This is due to the complexity of clinical decision-making, time pressure, and diagnostic uncertainty, which contribute substantially to medico-legal exposure. In this context, malpractice-related stress has been conceptualized within the framework of Medical Malpractice Stress Syndrome (MMSS), encompassing a descriptive construct of psychological and somatic manifestations that may impair professional performance and well-being. However, MMSS does not currently represent a uniformly defined clinical entity supported by standardized diagnostic criteria. The present review aims to examine the current evidence on malpractice-related stress among physicians in these high-intensity clinical environments, with particular focus on psychological outcomes, behavioral adaptations, and occupational consequences. The available evidence was heterogeneous and was concentrated primarily in emergency and acute-care settings, with limited trauma-specific evidence. Materials and Methods: This scoping review was conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR). The bibliographic search was carried out in April 2026 using databases including PubMed and Google Scholar, applying the following search strings: “malpractice AND physician stress AND emergency”, “malpractice stress AND ER”, and “malpractice stress AND trauma care”. Inclusion criteria included English-language studies focusing on physicians in acute care settings and evaluating psychological, behavioral, or occupational outcomes related to malpractice exposure. Exclusion criteria included absence of full text, lack of primary empirical data, or a focus limited to legal aspects without assessment of physician well-being. A two-stage screening process was applied. Results: The search strategy identified 1901 records, of which 7 studies met the predefined eligibility criteria. The available evidence indicated associations between malpractice-related exposure or fear of litigation and adverse psychological and occupational outcomes, including burnout, reduced job satisfaction, procedural anxiety, and changes in clinical behavior. Defensive medical practices and changes in clinical decision-making, including increased diagnostic testing and more conservative decision-making in some studies, were also reported. Evidence regarding supportive interventions was limited, with one pilot study providing preliminary information on the feasibility and potential value of structured peer support rather than evidence of effectiveness. Discussion: The findings of this review suggest that malpractice-related stress may represent a multidimensional occupational phenomenon associated with psychological and behavioural outcomes. Beyond its legal dimension, malpractice exposure has been associated with burnout and changes in clinical decision-making. The contextual literature has discussed broader implications of defensive medicine, although these system-level effects were not directly established by the included studies. Overall, the findings support further investigation of malpractice-related stress and of potential approaches to physician well-being and healthcare quality. Conclusions: Malpractice-related stress is increasingly recognized as an occupational factor associated with physician burnout, psychological distress, reduced job satisfaction, and defensive medicine in acute care and emergency settings, potentially affecting healthcare quality and patient safety. Further investigation of malpractice-related stress within the proposed MMSS descriptive framework may help inform the development of preventive psychological and organizational interventions. Despite limited and heterogeneous evidence, current findings highlight the need for greater institutional awareness and further longitudinal, multicenter research to better define causal relationships and evaluate targeted support strategies for physicians in high-risk clinical environments.

Trauma Care

26 October 2026
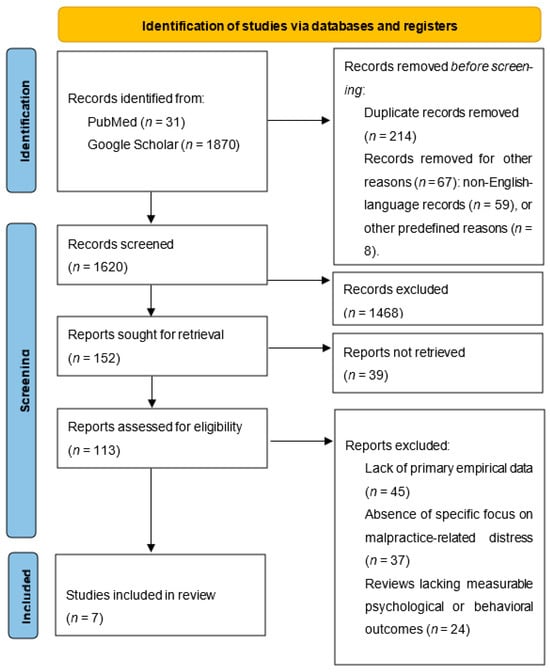
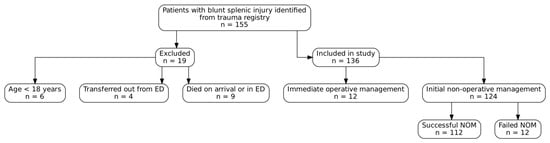
PRISMA flow diagram illustrating the study selection process.
  • Review
  • Open Access

Wound Ballistics of Craniocerebral Firearm Injuries

  • Panagiotis K. Stefanopoulos,
  • Konstantina Sotiropoulou and
  • Georgios Mikros
  • + 5 authors

Craniocerebral firearm injuries are associated with high mortality rates as a result of the kinetic energy deposition during the projectile–tissue interaction and its consequences, causing immediate and delayed brain damage. Ballistic factors that contribute to brain injury from bullets are related to the behavior of the projectile (whether it yaws, tumbles, mushrooms or disintegrates following skull penetration) and the creation of bone fragments from the entry site. Pressure waves generated intracranially associated with the temporary cavitation are the hallmark of bullet penetration of the head. Because of the absence of any compensatory mechanism to absorb the transient pressure loading, the largely incompressible brain tissue is subjected directly to its effects. The sudden increase in intracranial pressure and the resultant deformation of the brain during cavitation contributes to the development of brain edema and may affect the cardiac and respiratory centers of the brainstem, even if not transected by the bullet trajectory. Shotgun injuries to the head at close range cause extensive destruction of the brain, usually with catastrophic results, because the pellets enter the cranial cavity bunched together, thus acting as a single projectile of large diameter and kinetic energy. Injuries from fragments present with multiple, more or less circular wounds of various depths, depending on the kinetic energy of the fragments. This review includes a conceptual temporal organization of factors that have a prognostic significance, including those related to projectile and energy transfer characteristics and their consequences.

Trauma Care

12 October 2026

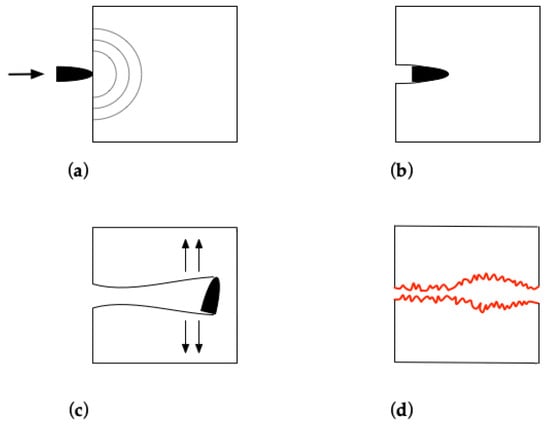
Schematic depiction of the various stages of the wounding process by penetrating projectiles: (a) initial impact, with shock wave propagation (indicated by hemicycles); (b) initiation of tissue penetration; (c) expanding temporary cavity formation in the wake of the tumbling bullet; (d) final appearance of the wound: permanent wound channel with irregular wound edges (shown in red) after collapse of the temporary cavity. The direction of the bullet motion is indicated by a solid arrow; vertical arrows indicate the expansion of the temporary cavity.
  • Article
  • Open Access

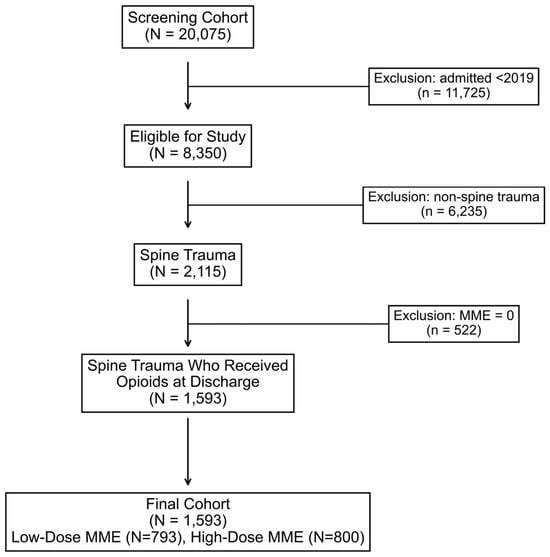
Background/Objectives: Opioid requirements among patients with spine trauma vary widely, yet the patient- and injury-level factors associated with high morphine milligram equivalent (MME) dosing at discharge remain unclear. This study aimed to characterize factors associated with high-dose MME at discharge. Methods: We conducted a retrospective cohort study of adult patients with spine trauma from 2019 to 2020. After excluding patients without spine trauma, 1593 patients with an opioid prescription at discharge were categorized into low-dose (below the cohort median MME) and high-dose (at or above the cohort median MME) groups. Patients in the high-dose group were propensity-score matched 1:3 to low-dose controls (with replacement) on age, sex, race, ethnicity, chronic opioid use, chronic pain syndrome, and other substance use. Within the matched cohort, a multivariable logistic regression model with cluster-robust standard errors was fitted to examine factors associated with high-dose MME (cutoff at 384). Covariates included spine trauma group (isolated vs. polytrauma, isolated as reference), injury severity score (ISS) stratum (ISS ≤ 15 as reference), head injury severity category, spine injury severity category, procedural status (non-surgical as reference), mechanical ventilation status (non-ventilated as reference), hospital length of stay, and discharge disposition (home/home health as reference, versus rehabilitation, nursing home, or other facility). Adjusted odds ratios (aORs) with 95% confidence intervals (CIs) were reported. Results: Of the 1593 patients included, 793 were in the low-dose MME group and 800 in the high-dose group. In the propensity-matched cohort, surgical procedures were associated with high-dose MME (aOR 1.52 [95% CI, 1.18–1.95]; p = 0.001). Discharge to inpatient rehabilitation (aOR 0.30 [95% CI, 0.14–0.64]; p = 0.002) and discharge to a nursing home (aOR 0.41 [95% CI, 0.30–0.56]; p < 0.001) were independently associated with lower odds of high-dose MME relative to home discharge. Spine trauma type, ISS stratum, head and spine injury severity category, mechanical ventilation, discharge to other facilities, and hospital length of stay were not associated with high-dose MME. Conclusions: This study demonstrates that discharge opioid prescribing in spine trauma is shaped more by procedural and discharge practices. These findings underscore the need for targeted opioid stewardship interventions at the points of surgical decision-making and discharge planning.

Trauma Care

13 September 2026

Study sample derivation flowchart.
  • Article
  • Open Access

Assessment of IV Contrast Utilization and Utility in the MRI Evaluation of Acute Spine Trauma

  • Ali R. Satchmei,
  • Karina F. Irani and
  • Kevin D. Hiatt
  • + 5 authors

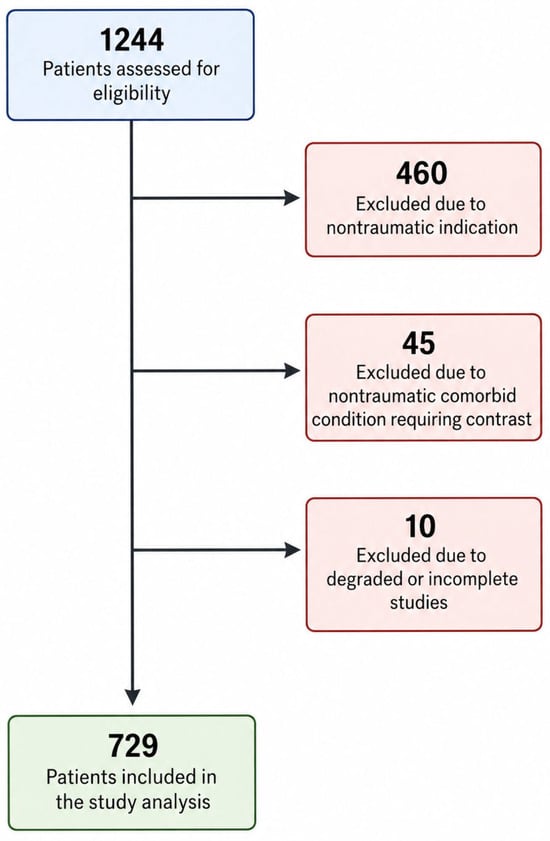
Purpose: MRI is a valuable tool in evaluating select acute spine trauma cases, offering superior assessment of soft tissue, ligament, and spinal cord injuries compared to CT and radiographs. Although the ACR Appropriateness Criteria advises MRIs be performed without gadolinium-based IV contrast, guidelines utilized by ordering physicians do not clarify the role of contrast. The downsides of IV contrast should be balanced against potential benefits. This study examined the frequency and value of contrast-enhanced MRI in acute spine trauma. Methods: An IRB-approved retrospective chart review of spine MRIs ordered for trauma between 2020 and 2022 was conducted at a level 1 trauma, academic medical center. Contrast-enhanced studies were reviewed by a neuroradiologist for clinically significant findings (fractures, ligamentous injuries, epidural hematoma, cord injury) visible only or more clearly on postcontrast imaging. Patient demographics, clinical and operative notes, ordering provider specialty, and preceding imaging were reviewed. Results: Of 729 eligible patients receiving MRIs (608 adult, 121 pediatric), 16.2% of studies were performed with contrast. Pediatric patients were more likely to have radiographs and less likely to have CTs performed before MRI. Pediatric patients were more likely to undergo contrast-enhanced MRIs than adults (32.2% vs. 13.0%). Hospitalists ordered contrast more frequently (61.5%) than surgery (14.2%), emergency medicine (12.6%), or internal medicine (21.2%) providers. No cases were identified where postcontrast imaging provided findings missed or less visible on precontrast imaging. Conclusions: The absence of added value from contrast-enhanced imaging supports ACR guidelines against routine contrast use in MRI assessment of spine trauma. Heterogeneous ordering practices highlight the need for provider education.

Trauma Care

4 September 2026

Flow diagram showing groups of patients excluded from the initial cohort. Blue shaded box: initial group of patients assessed. Red shaded boxes: patients excluded from the study, grouped by reason. Green shaded box: patients included in the study.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Trauma Care - ISSN 2673-866X