


Abstract
Stroke and brain cancer are severe disorders of the central nervous system (CNS) associated with high morbidity and mortality. Although each condition has been extensively studied individually, growing evidence suggests that cerebrovascular injury may influence the development of brain malignancies. This narrative review synthesizes current experimental, clinical, and epidemiological data supporting a mechanistic link between stroke and brain cancer, with a particular focus on blood–brain barrier (BBB) dysfunction. We discuss how stroke-induced hypoxia, oxidative stress, and neuroinflammation disrupt BBB integrity, promote endothelial activation, and induce the expression of adhesion molecules that facilitate arrest, extravasation, and survival of circulating tumor cells within the CNS. Additionally, post-stroke regenerative signaling, angiogenesis, and immune modulation may contribute to the formation of a permissive microenvironment that supports tumor initiation and metastatic growth. Available epidemiological studies, clinical observations, and case reports are reviewed to evaluate the strength and limitations of the association between cerebrovascular events and subsequent brain cancer. Although the co-occurrence of stroke and brain cancer remains relatively uncommon, elucidating the shared molecular and cellular mechanisms underlying this relationship can improve risk stratification and allow the development of diagnostic and therapeutic strategies aimed at preserving BBB integrity and reducing long-term oncological complications after stroke.
1. Introduction
Advances in medical and biological research have substantially extended human life expectancy; however, this increased longevity has been accompanied by a growing burden of debilitating diseases. Among non-communicable disorders, cerebrovascular accidents—commonly referred to as strokes—remain a leading cause of mortality and long-term disability worldwide, ranking third overall. Epidemiological projections indicate that up to one in four individuals will experience a stroke during their lifetime [1]. Clinically, strokes are broadly classified into ischemic stroke (IS), resulting from cerebral vessel occlusion, and hemorrhagic stroke (HS), characterized by intracerebral or subarachnoid bleeding. In addition, transient ischemic attacks (TIAs) represent episodes of cerebral ischemia without radiological evidence of acute infarction [2]. Despite their heterogeneity, all major stroke subtypes share a common pathophysiological consequence—disruption of the neurovascular unit (NVU) and impairment of blood–brain barrier (BBB) integrity—which can persist beyond the acute phase and influence long-term tissue remodeling.
For clarity, several related but conceptually distinct terms used throughout this review require brief definitions. The BBB denotes the highly specialized endothelial interface that regulates molecular and cellular exchange between the systemic circulation and the healthy central nervous system. Disruption of the BBB refers to the loss of its structural and functional integrity, a phenomenon commonly observed after cerebrovascular injury, including IS and hemorrhagic stroke (HS). In contrast, the blood–tumor barrier (BTB) represents a pathologically remodeled and spatially heterogeneous vascular interface that emerges within primary brain tumors or metastatic lesions and differs from the physiological BBB in permeability, transporter expression, and cellular composition.
Beyond endothelial alterations, neurovascular unit (NVU) dysfunction encompasses coordinated changes across multiple cellular components—including endothelial cells, pericytes, astrocytes, microglia, neurons, and the extracellular matrix—that collectively regulate cerebrovascular stability and brain homeostasis. In the context of stroke and brain cancer, BBB disruption, BTB formation, and NVU dysfunction should be viewed as interconnected but temporally and mechanistically distinct processes that together shape a microenvironment permissive to tumor initiation, progression, and metastatic colonization.
In parallel with cerebrovascular disorders, the incidence of brain tumors is expected to increase with progressive population ageing. Brain tumors may arise within the CNS as primary malignancies, including gliomas and astrocytomas, or develop as secondary lesions through metastasis of peripheral tissues. According to the most recent epidemiological reports, the incidence of brain cancer in the United States is approximately 25.34 per 100,000 individuals. Of these cases, approximately 73% are classified as non-malignant, whereas 27% are malignant [3]. Notably, more than half of malignant tumors correspond to World Health Organization grade IV astrocytomas, namely glioblastoma, which remains associated with a dismal prognosis, with only approximately 25% of patients surviving beyond two years following initiation of treatment [4]. Current standard-of-care therapy combines surgical resection, radiotherapy, and chemotherapy; nevertheless, median overall survival remains limited to approximately 14 months [5]. Given that global mortality rates from brain tumors have remained largely unchanged since 1990, there is a pressing need for novel therapeutic strategies and improved approaches to early diagnosis [6]. Importantly, the poor prognosis of malignant brain tumors is closely linked not only to their intrinsic aggressiveness but also to the presence of the BBB, which acts as both a physical and biological barrier influencing tumor evolution, immune interactions, and therapeutic accessibility.
In recent years, increasing attention has been directed towards the shared molecular mechanisms underlying stroke and brain cancer, raising the possibility of a bidirectional relationship between these conditions [7,8,9,10,11,12,13,14,15,16]. Although previous studies and reviews have described epidemiological associations and overlapping risk factors between cerebrovascular disease and malignancy, these analyses have remained largely descriptive or focused on systemic mechanisms. Notably, the BBB has been discussed primarily either as a victim of cerebrovascular injury or as an obstacle to drug delivery in brain tumors, rather than as an active mechanistic interface dynamically linking post-stroke pathophysiology with tumor initiation and metastatic permissiveness. Consequently, although experimental, clinical, and epidemiological data supporting interactions between stroke and brain cancer are accumulating, an integrative framework that positions BBB dysfunction as a central mediator of this axis remains lacking.
Therefore, this review aims to highlight the BBB as a critical and dynamic mediator of pathogenic processes triggered by cerebrovascular injury and to discuss the molecular and cellular pathways through which stroke-induced BBB dysfunction may contribute to the development of primary and metastatic CNS tumors. We propose that sustained alterations of BBB integrity after stroke can create a tumor-permissive microenvironment, providing mechanistic plausibility for increased vulnerability to brain tumor development or metastatic seeding, while acknowledging that current evidence remains largely associative and hypothesis-generating rather than causally definitive. By integrating mechanistic insights, epidemiological observations, and emerging translational perspectives, this review seeks to delineate unresolved controversies and identify priority areas for future research at the intersection of cerebrovascular disease, BBB biology, and neuro-oncology.
2. Blood–Brain Barrier
The BBB is a highly specialized and dynamic interface that regulates molecular exchange between the CNS and the systemic circulation while preserving neural homeostasis. It ensures controlled transport of essential nutrients, including glucose, amino acids, nucleotides, and selected neurotransmitters, while simultaneously protecting neural tissue from toxic metabolites, pathogens, and xenobiotics. Beyond its classical barrier function, the BBB actively participates in metabolic regulation, immune surveillance, and neurovascular signaling.
Structurally, the BBB is formed by non-fenestrated brain microvascular endothelial cells interconnected by complex junctional systems and supported by a specialized basement membrane, pericytes, astrocytic endfeet, vascular smooth muscle cells, and associated immune and glial components of the NVU [17]. Endothelial cells line the cerebral capillaries and are interconnected by tight junctions (TJs), which restrict paracellular diffusion and confer the high electrical resistance characteristic of the barrier. TJs consist of transmembrane proteins, including claudins, occludin, and junctional adhesion molecules (JAMs) [18], which are anchored to the actin cytoskeleton via zona occludens (ZO) proteins [19]. Contrary to earlier assumptions, TJs are not static structures but undergo continuous remodeling in response to physiological stimuli and pathogenic processes [20]. Their stability and organization are further supported by adherent junctions (AJs), primarily composed of E-, N-, and VE-cadherins, which not only contribute to barrier cohesion but also regulate the expression and localization of the TJ components [18]. Disruption or downregulation of these junctional complexes increases permeability of the BBB, with claudin-5 recognized as a key determinant of paracellular tightness in cerebral vessels [15,19,20].
In parallel, BBB endothelial cells express a range of ATP-binding cassette (ABC) transporters, including P-glycoprotein (P-gp), multidrug resistance-associated proteins (MRPs), and breast cancer resistance protein (BCRP), which actively extrude xenobiotics and metabolic waste products back into the bloodstream [19,21]. This efflux system constitutes a critical protective mechanism; however, it also represents a major obstacle to effective CNS drug delivery.
The integrity of the BBB is further reinforced by pericytes embedded within the basement membrane. Together with vascular smooth muscle cells, pericytes regulate cerebral blood flow through contractile activity [22] and contribute to vessel stabilization. Importantly, pericytes play a central role in maintaining the integrity of the BBB, modulating endothelial gene expression, and shaping the local inflammatory environment through the release of cytokines and signaling molecules [23].
Astrocytes form the outer cellular layer of the BBB and exert profound regulatory effects on barrier function. Their terminal processes, known as endfeet, ensheathe brain microvessels and interact closely with endothelial cells and pericytes, providing mechanical support to the basement membrane [23,24,25]. Astrocytes express key channels and transporters, including potassium channels and aquaporin-4 (AQP4), which regulate ion and water homeostasis and thus contribute to the balance of cerebrospinal fluid (CSF) [25]. Moreover, astrocytes can attenuate microglial activation and promote BBB repair under certain conditions, highlighting their role in barrier regeneration [26]. Experimental transplantation studies further demonstrate that astrocytes can induce BBB-like properties in non-CNS vasculature, underscoring their importance in barrier formation and maintenance [27].
Together, endothelial cells, pericytes, astrocytes, junctional complexes, and associated extracellular matrix components constitute the neurovascular unit (NVU)—a functional and clinically relevant entity that integrates vascular, neuronal, and glial signaling [28]. NVU dysfunction is a hallmark of numerous neurological disorders, including ischemic stroke, traumatic brain injury, Alzheimer’s disease, and subarachnoid hemorrhage, all of which are characterized by varying degrees of BBB disruption [29]. Consequently, the BBB should be viewed not merely as a passive barrier but as an active regulator of CNS homeostasis, whose dysregulation represents a central pathogenic event in neurological and neuro-oncological disorders.
3. Stroke-Induced Mechanisms of BBB Dysfunction
Stroke encompasses a heterogeneous group of cerebrovascular events that differ in etiology and clinical presentation but share a common pathological hallmark—disruption of BBB integrity. Whether caused by ischemia, hemorrhage, or transient hypoperfusion, stroke induces a complex cascade of metabolic, inflammatory, and vascular responses that compromise endothelial function and alter neurovascular homeostasis. Increasing evidence indicates that BBB dysfunction not only contributes to acute neuronal injury but may also persist beyond the initial insult, thus shaping long-term neurological outcomes and creating a permissive microenvironment for secondary pathological processes. The exact interplay between the diseases discussed and their molecular mechanisms is summarized in Figure 1.
Figure 1.
Stroke-induced BBB (blood–brain barrier) disruption and its effects on tumorigenesis. Ischemic stroke (IS) is usually caused by thrombus occluding brain blood vessels. Sudden hypoperfusion triggers the release of reactive oxygen species (ROS) resulting in oxidative stress, leading to apoptosis of endothelial cells. Additionally, ROS-mediated DNA damage can be a driver for oncogenic mutations. In hemorrhagic stroke (HS) oxidative stress plays a more substantial role, as it is further exacerbated by heme toxicity and plasmin signaling pathways. Tissue damage also activates release of inflammatory cytokines that attract immune cells. Activated endothelial cells present adhesive molecules, such as E-selectins, vascular cell adhesion molecule 1 (VCAM-1) and activated leukocyte cell adhesion molecule (ALCAM), allowing lymphocytes and macrophages to enter the central nervous system (CNS). Their presence can either amplify or reduce the immune response. In response to ischemia, hypoxic response mediated by hypoxia inducible factor 1 a (HIF-1a) triggers the release of factors (vascular endothelial growth factor (VEGF), platelet derived growth factor receptor β (PDGFRβ)) that are responsible for cell survival and angiogenesis. All these processes result in disruption of BBB, mediated by activation of matrix metalloproteinases (MMP) and down regulation of endothelial tight junctions. Described processes create a favorable tumor microenvironment, supporting a pre-metastatic niche or allowing primary neoplasms to develop.
BBB dysfunction represents a central pathological characteristic in the spectrum of cerebrovascular events, including IS, HS, and TIA. Although these conditions are driven by distinct initiating mechanisms, they converge on endothelial injury, inflammatory activation, and loss of BBB integrity, collectively contributing to acute neuronal damage and long-term neurological deterioration [30].
In IS, oxygen and glucose deprivation initiate a cascade of enzymatic and oxidative processes that progressively compromise vascular integrity. Early after ischemia, increased activity of matrix metalloproteinases (MMP-3, MMP-9, and MMP-12) leads to degradation of key components of the basement membrane and TJ complexes, a process further amplified by pro-inflammatory cytokines such as tumor necrosis factor α (TNF-α) and interleukins (IL’s), including IL-1β, and IL-6, as well as by reactive oxygen species (ROS) [31,32,33]. Consequently, paracellular permeability increases, facilitating rapid influx of peripheral immune cells into the CNS and promoting secondary neuroinflammation [32,34,35]. Beyond structural leakage, ischemia also profoundly alters the transport function of the BBB. Dysregulation of influx and efflux transporters results in the accumulation of toxic metabolites and impaired delivery of neuroprotective substrates, including glucose and antioxidants, thereby reducing neuronal resilience and complicating pharmacological intervention [31].
The loss of BBB integrity further predisposes ischemic tissue to hemorrhagic transformation. Extravasation of blood into the brain parenchyma causes mechanical compression, while hemoglobin, heme, and iron released from lysed erythrocytes act as potent drivers of oxidative stress, lipid peroxidation, and endothelial apoptosis [36]. Thrombin—derived both from vascular leakage and local production by neurons and astrocytes—plays a pivotal role in secondary injury. Through activation of protease-activated receptors (PARs), particularly PAR-1, thrombin induces cytoskeletal remodeling, intracellular calcium influx, and degradation of TJs, thereby amplifying vasogenic edema [36,37]. In parallel, thrombin enhances the release of pro-inflammatory cytokines, stimulates further activation of MMPs, and directly converts IL-1α into its active form, effectively coupling the coagulation cascade with neuroinflammatory signaling pathways [38].
Although transient and non-fatal by definition, TIAs are increasingly recognized as events capable of inducing subtle yet persistent BBB dysfunction. Brief episodes of cerebral hypoperfusion can trigger endothelial activation and low-level oxidative and enzymatic responses resembling those observed in IS. Clinical studies demonstrate that patients with a history of TIA exhibit elevated serum concentrations of platelet-derived growth factor receptor β (PDGFRβ)—a proposed biomarker of pericyte injury and BBB leakage—as well as increased expression of endothelial adhesion molecules, including vascular cell adhesion molecule 1 (VCAM-1) [39] and intercellular adhesion molecule 1 (ICAM-1) [40]. These molecules promote leukocyte adhesion and transmigration, reflecting an early and potentially reversible stage of barrier compromise. Importantly, the same adhesion pathways are exploited during brain metastasis, where they facilitate the docking and extravasation of circulating tumor cells (CTCs), thereby establishing a plausible mechanistic link between cerebrovascular injury and tumor dissemination [41,42,43,44], which requires further validation in dedicated studies.
In summary, the distinct pathophysiological mechanisms underlying IS, HS, and TIA give rise to disease-specific patterns of BBB dysfunction. In IS, hypoxia-driven oxidative stress initiates activation of MMPs, release of inflammatory cytokines, and degradation of TJ proteins of the tight junction, such as claudin-5 and occludin. HS, by contrast, is characterized by an abrupt and profound loss of barrier integrity, followed by cytotoxic effects of extravasated blood components. Hemoglobin, heme, and iron promote oxidative injury, while thrombin-mediated PAR activation and widespread neuroinflammation exacerbate endothelial damage and vasogenic edema. Although TIA does not result in permanent infarction, accumulating evidence indicates that even transient hypoperfusion can induce persistent, low-grade BBB alterations that may contribute to long-term cerebrovascular vulnerability. The key mechanisms underlying BBB disruption across IS, HS, and TIA are summarized in Table 1.
Table 1.
Collection of BBB degradation mechanisms in different types of strokes. Meaning of symbols: “+”—mechanism leads to disruption of BBB, “−”—mechanism not present/does not influence BBB permeability.
3.1. Oxidative Stress
Oxidative stress refers to a pathological condition in which the production of ROS and reactive nitrogen species (RNS) exceeds the antioxidant capacity of the cell, leading to oxidative damage to DNA, lipids, and proteins [45]. Despite their cytotoxic potential, ROS are integral components of normal cellular metabolism and play essential roles in redox signaling. Physiological sources of ROS include oxidative phosphorylation within the mitochondrial electron transport chain, β-oxidation in peroxisomes, and cytochrome P450–mediated metabolism. Under homeostatic conditions, intracellular redox balance is maintained by antioxidant defense systems, including superoxide dismutase (SOD), glutathione peroxidase (GPx), and catalase [46].
Oxidative stress is a well-established driver of tumorigenesis, as excessive DNA oxidation promotes genomic instability and mutagenesis. ROS and RNS can directly interfere with proto-oncogenes, such as cyclin-dependent kinase 4/6 (CDK4/6), and tumor suppressor genes, including tumor protein p53 (TP53) [47]. Concurrently, ROS activate major pro-survival and pro-proliferative signaling pathways—including MAPKs, the Akt/NF-κB axis, mTOR, TGF-β, and AMPK—thereby promoting cellular proliferation, inhibiting apoptosis, and facilitating tumor progression [47,48,49,50,51,52,53]. These pathways are particularly relevant in glioblastoma, where dysregulation of Akt–mTOR signaling is frequently observed due to loss-of-function mutations in PTEN [54].
Additional evidence indicates that ROS act downstream of epidermal growth factor receptor (EGFR) signaling, modulating DNA-dependent protein kinase (DNA-PK) interactions with p53 and leading to functional suppression of p53-mediated apoptosis [48]. ROS have also been implicated in EGFR-driven cytoskeletal remodeling and enhanced motility of GBM cells—processes essential for local invasion and metastatic dissemination [55,56]. Importantly, these tumor-promoting effects of oxidative stress gain particular relevance in the post-stroke brain, where sustained ROS production coincides with compromised BBB integrity and altered neurovascular homeostasis.
Beyond Akt-dependent pathways, ROS activate c-Jun N-terminal kinase (JNK) signaling. JNK activation promotes the proliferation and tumorigenicity of glioma stem cells [57]. At the same time, JNK signaling contributes to BBB disruption by inducing apoptosis in endothelial cells and oligodendrocytes, promoting tight junction degradation, and amplifying neuroinflammatory responses [57]. This dual role of JNK signaling—enhancing tumor aggressiveness while impairing BBB integrity—creates conditions permissive for metastatic spread, as demonstrated in experimental models of non-small cell lung cancer (NSCLC) brain metastasis [58].
In response to oxidative stress, endothelial cells secrete a range of pro-inflammatory cytokines, including TNF-α, IL-1β, IL-6, IL-17, and TGF-β. These mediators induce the expression of endothelial adhesion molecules, such as P- and E-selectins and ICAM-1 [47,59]. Circulating tumor cells can exploit these adhesion pathways to initiate vascular arrest, extravasation, and metastatic colonization of the brain [60,61]. Furthermore, cytokine-mediated activation of nicotinamide adenine dinucleotide phosphate (NADPH) oxidase and xanthine oxidase, along with other signaling pathways [7], establishes a positive feedback loop that sustains oxidative stress within the post-stroke neurovascular microenvironment, thereby further weakening BBB integrity and facilitating CNS invasion by metastatic cells.
Paradoxically, excessive ROS accumulation can also activate apoptotic pathways and induce mitophagy, thereby limiting tumor progression [7,59]. Cellular adaptation to oxidative stress is largely mediated by nuclear factor erythroid 2–related factor 2 (NRF2), which regulates the expression of antioxidant enzymes such as GPx and SOD. While NRF2 activity may exert tumor-suppressive effects under physiological conditions, its sustained activation in cancer has been associated with therapy resistance and poor clinical outcomes, highlighting the context-dependent role of redox signaling in oncology [47,62,63].
In the setting of cerebrovascular injury, oxidative stress represents a primary driver of BBB dysfunction rather than a secondary epiphenomenon. During ischemia–reperfusion injury, reoxygenation triggers excessive production of ROS, including superoxide anions, hydroxyl radicals, hydrogen peroxide, and peroxynitrite [33]. These reactive species compromise BBB integrity through lipid peroxidation, protein oxidation, endothelial apoptosis, and activation of matrix metalloproteinases MMP-2 and MMP-9, leading to degradation of the basement membrane and tight junction complexes and increased BBB permeability [31,34].
Collectively, these oxidative stress–driven mechanisms disrupt the BBB at both cellular and paracellular levels, creating a permissive microenvironment that may support primary tumor initiation as well as metastatic colonization within previously injured brain regions. Key ROS-responsive signaling pathways that link oxidative stress with BBB disruption and glioma progression are summarized in Table 2.
Table 2.
Summary of ROS-activated pathways responsible for the growth of primary and metastatic brain tumors.
Taken together, oxidative stress emerging after cerebral ischemia or hemorrhage represents a critical driver of BBB dysfunction rather than an isolated byproduct of tissue injury. In the post-stroke setting, excessive reactive oxygen species directly compromise endothelial tight junction integrity, promote endothelial activation, and enhance BBB permeability. These alterations facilitate the adhesion and transmigration of circulating tumor cells and may also support malignant transformation within vulnerable brain regions by sustaining a pro-oxidative, DNA-damaging microenvironment. Thus, oxidative stress constitutes a mechanistic bridge linking acute cerebrovascular injury with long-term tumor-permissive BBB alterations.
3.2. Neuroinflammation
Neuroinflammation is an inflammatory response within the CNS that is frequently initiated by oxidative stress and tissue injury [64,65]. A defining feature of this process is the activation of glial cells, which leads to the release of pro-inflammatory cytokines such as TNF-α and multiple interleukins [25,66,67]. These mediators profoundly influence neurovascular homeostasis by modulating endothelial function, immune cell recruitment, and the structural and functional integrity of the BBB.
TNF-α–activated astrocytes engage the signal transducer and activator of transcription 3 (STAT3) signaling pathway, which plays a pivotal role in the post-stroke formation of a tumor-promoting microenvironment by enhancing immunosuppression and compromising BBB integrity. This signaling cascade facilitates tumor cell survival and invasion and contributes to the establishment of a microenvironment favorable for metastatic dissemination. Notably, TNF-α may also be secreted by tumor cells, further amplifying inflammatory signaling within the already vulnerable post-ischemic brain microenvironment [68].
Following IS, microglia rapidly adopt an activated phenotype, reflecting an early and robust inflammatory response. Ju et al. demonstrated that extravasation of blood significantly intensifies microglial activation, underscoring the close relationship between vascular injury and immune signaling [69]. In parallel, endothelial cells, microglia, and astrocytes secrete interferon-induced protein 35 (IFP35) in response to acute ischemia. Through activation of the NF-κB pathway, IFP35 sustains and amplifies inflammatory signaling within NVU [70].
Activation of the RelA/NF-κB axis in microglia has been associated with enhanced metastatic potential in experimental models, including melanoma brain metastasis [71]. In contrast, therapeutic targeting of this pathway can shift microglial polarization toward a more pro-inflammatory and antitumor phenotype. In brain microvascular endothelial cells, NF-κB activation induces downregulation of TJ proteins—particularly claudin-5 and occludin—leading to BBB destabilization [66,72]. Importantly, BBB disruption not only results from neuroinflammation but also perpetuates it, as increased permeability facilitates the entry of plasma proteins and peripheral immune cells into the CNS, thereby reinforcing inflammatory signaling loops and sustaining a tumor-permissive microenvironment [25,66].
Oligodendrocyte precursor cells (OPCs), which are closely associated with brain microvascular endothelial cells [25], contribute to BBB stability through the secretion of TGF-β1. This cytokine promotes the expression of TJ-associated proteins, including ZO-1, occludin, and claudin-5, in endothelial cells. However, OPC migration along blood vessels can displace astrocytic endfeet and disrupt astrocyte–endothelial interactions, as demonstrated in three-dimensional in vitro models [73,74]. Moreover, OPC activity triggers neuroinflammatory signaling, activates microglia, and promotes the recruitment of macrophages and T lymphocytes from the peripheral circulation [74,75], collectively weakening BBB integrity in the post-stroke setting.
Pericytes further modulate BBB responses during post-ischemic neuroinflammation by secreting neurotrophic and pro-angiogenic factors, including BDNF and pleiotrophin (PTN), which support endothelial survival but simultaneously activate NF-κB signaling, angiogenesis, and tumor-associated pathways observed in gliomas [76,77,78,79].
Breakdown of the BBB enables infiltration of circulating immune cells into the CNS, a process tightly regulated by chemokines released from glial and vascular cells. Astrocyte-, microglia-, and pericyte-derived chemokines such as MCP-1, CXCL1, and macrophage inflammatory proteins regulate immune cell recruitment, vascular remodeling, and sustained inflammatory signaling [32,67,80,81,82,83,84,85,86]. Collectively, these chemokine-driven processes amplify neuroinflammation, compromise BBB integrity, and facilitate immune evasion and metastatic colonization within the CNS [23,83,87,88,89,90,91].
The key neuroinflammatory mediators involved in BBB dysfunction and the establishment of a permissive tumor microenvironment following cerebrovascular injury are summarized in Table 3.
Table 3.
Neuroinflammatory mediators contributing to BBB dysfunction and permissive tumor microenvironment following cerebrovascular injury.
In the context of stroke, neuroinflammation extends beyond transient immune activation and becomes a sustained modifier of BBB structure and function. Activated microglia, infiltrating immune cells, and pro-inflammatory cytokines synergistically disrupt endothelial junctions and promote the expression of adhesion molecules on BBB endothelial cells. This inflammatory remodeling enhances vascular permeability and creates a permissive interface for tumor cell arrest, extravasation, and immune evasion within the CNS. Consequently, post-stroke neuroinflammation provides a direct and mechanistically relevant link between cerebrovascular injury, persistent BBB dysfunction, and increased oncological vulnerability of the brain.
Collectively, these findings highlight a self-reinforcing neurovascular network in which interactions among glial and vascular cells drive sustained neuroinflammation and progressive BBB dysfunction. Persistent activation of this inflammatory axis not only exacerbates post-ischemic injury but also actively shapes a tumor-permissive microenvironment that may facilitate tumor invasion and metastatic dissemination within the CNS. Importantly, many of these inflammatory and angiogenic pathways are further potentiated under hypoxic conditions, which represent a convergent driver of BBB dysfunction following cerebrovascular injury.
3.3. Hypoxia
Hypoxia, defined as a state of insufficient oxygen availability at the tissue level, represents a central pathophysiological link between cerebrovascular injury and brain cancer. It may arise as a consequence of ischemia following stroke or as a result of high metabolic demand and insufficient vascularization within rapidly growing tumors [107]. Hypoxia-inducible factor 1 (HIF-1) is the main transcriptional regulator of cellular adaptation to reduced oxygen availability. Under normoxic conditions, the HIF-1α subunit undergoes rapid proteasomal degradation, whereas hypoxia stabilizes HIF-1α, allowing its translocation to the nucleus and transcriptional activity. HIF-1α expression can also be enhanced by ROS [26] and by growth factor–dependent signaling pathways involving vascular endothelial growth factor (VEGF), PDGF, and angiopoietins (Ang-1/Ang-2) [95,108], thereby integrating hypoxic and post-stroke inflammatory cues within the neurovascular unit.
Through regulation of more than one hundred target genes, HIF-1α exerts pleiotropic effects that include cell survival, angiogenesis, metabolic reprogramming [103,108], and inflammatory signaling [109]. In the context of IS, HIF-1α plays a dual role in BBB regulation. While certain HIF-1α–dependent pathways confer neuroprotection, others contribute to barrier destabilization. Canonical HIF-1α targets include erythropoietin (EPO) and glucose transporter 1 (GLUT1), which promote oxygen delivery and metabolic support to hypoxic tissues [7]. Notably, these adaptive responses may be co-opted in the post-stroke brain to support tumor cell survival and growth. Downstream HIF-1α targets such as GLUT1/3, VEGF, EPO, and BCL2/adenovirus E1B 19 kDa-interacting protein 3 (BNIP3) enhance glucose uptake, angiogenesis, and metabolic flexibility in cancer cells [7,48]. In parallel, HIF-1α suppresses apoptotic signaling by inhibiting cytochrome c release, poly(ADP-ribose) polymerase (PARP) cleavage, and p53 activation, thereby promoting tumor cell survival [7].
Despite its adaptive functions, HIF-1 signaling has profound disruptive effects on BBB integrity. Experimental BBB models demonstrate that HIF-1α activates downstream pathways such as RhoA/ROCK-1/-2 and myosin light-chain kinase (MLCK), leading to cytoskeletal reorganization and subsequent disassembly of tight junction proteins, including claudin-5 and occludin [110]. Additional mechanisms of BBB disruption involve hypoxia-induced overexpression of matrix MMP-9, which degrades both TJs and components of the basement membrane [96]. Clinical evidence supports these findings: Wu et al. reported that elevated levels of HIF-1α in patients with intracerebral hemorrhage were positively correlated with TNF-α expression and inversely correlated with ZO-1 levels in peripheral blood mononuclear cells, reflecting molecular changes associated with BBB impairment, later confirmed in rat models [107].
In endothelial cells and astrocytes, HIF-1α drives upregulation and secretion of VEGF [109]. VEGF promotes sprouting angiogenesis, a process closely resembling tumor neovascularization. The binding of VEGF to vascular endothelial growth factor receptor 2 (VEGFR2) activates endothelial cells and induces detachment of pericytes from the basal lamina and extracellular matrix [101] or pericyte apoptosis [105]. Concurrently, endothelial cells downregulate the expression of tight junction proteins such as claudin-5 and ZO-1 [106], further compromising barrier integrity. Similar mechanisms have been described in gliomas, where tumor-derived exosomes containing VEGF exacerbate BBB disruption [111]. Moreover, VEGF-induced secretion of MMP-2 and MMP-9 by neurovascular unit cells accelerates degradation of the basement membrane and endothelial TJs [105,107,109]. Collectively, these hypoxia-driven processes converge on BBB destabilization, promote vasogenic edema, and create conditions that are permissive for tumor cell extravasation into the brain parenchyma [112].
Beyond BBB disruption, post-stroke hypoxia creates a favorable microenvironment for tumor development and progression. HIF signaling is a major driver of GBM pathogenesis. Acting downstream of AMPK, HIF-1α induces the expression of glucose transporters (GLUT1/3), glycolytic enzymes (hexokinase 2, 6-phosphofructo-2-kinase/fructose-2,6-bisphosphatase), and enzymes involved in serine and glycine biosynthesis. Activation of this metabolic program has been correlated with a poor prognosis in patients with GBM [48]. Hypoxia also promotes the establishment of an immunosuppressive tumor microenvironment characterized by the accumulation of regulatory T cells (Tregs), myeloid-derived suppressor cells (MDSCs), and polarization of tumor-associated macrophages toward the M2 phenotype [113,114]. Furthermore, HIF-1α enhances immune evasion by upregulating VEGF/VEGFR signaling and inducing expression of programmed death ligand 1 (PD-L1), thereby impairing T-cell–mediated antitumor responses. Additional HIF-1α–regulated genes, including cyclooxygenase-2 (COX-2), hypoxia-inducible gene 2 (HIG2), and galactosylceramide sulfotransferase 1 (GAL3ST1), further enable cancer cells to escape NK cell–mediated cytotoxicity [115]. Figure 2 portrays the interplay of hypoxia-related signaling pathways.
Figure 2.
Scheme summarising hypoxic mechanisms responsible for cancer development.
Although hypoxia-induced responses initially support tissue repair following stroke, these same mechanisms may inadvertently foster a tumor-permissive microenvironment by promoting angiogenesis, increasing nutrient availability, and weakening BBB integrity.
Post-stroke hypoxia represents a potent and sustained stimulus for BBB remodeling with direct relevance to tumor biology. Hypoxia-driven activation of HIF-dependent signaling pathways alters endothelial metabolism, downregulates tight junction proteins, and promotes angiogenic and pro-survival responses within the neurovascular unit. These changes not only compromise BBB integrity but also generate a microenvironment that mirrors key features of the tumor niche, including metabolic reprogramming and immune suppression. As a result, hypoxia serves as a unifying mechanism through which stroke-induced BBB dysfunction may facilitate both primary tumor initiation and metastatic colonization of the brain.
4. Stroke-Induced BBB Dysfunction as a Driver of Brain Metastasis
Brain metastases represent the most common intracranial malignancies and affect approximately one in four patients with selected primary cancers, particularly melanoma and lung cancer [116]. Despite their clinical relevance, the mechanisms underlying the organ-specific tropism of CTCs toward the brain remain incompletely understood. The predominant “seed and soil” hypothesis posits that metastatic colonization depends on reciprocal interactions between disseminated tumor cells (“seeds”) and a permissive organ microenvironment (“soil”) [117]. In this context, stroke-induced alterations of the cerebral microvasculature and BBB integrity may critically reshape the brain microenvironment, facilitating metastatic seeding and outgrowth.
To establish secondary tumors within the brain, CTCs must cross the BBB through a multistep process that closely resembles leukocyte transendothelial migration [118]. The initial step involves transient interactions between CTCs and endothelial adhesion molecules, leading to rolling and deceleration of tumor cells along the cerebral microvasculature. This process is mediated primarily by endothelial E- and P-selectins [60,119].
Importantly, IS induces robust endothelial activation characterized by upregulation of selectins, including CD62E, largely driven by inflammatory cytokines such as TNF-α. Elevated expression of E-selectins has been shown to promote brain metastasis of NSCLC [120]. Rai et al. further demonstrated that NSCLC cells release factors—including cystatin C, cathepsin L, VEGF, and TNF-α—that enhance tumor cell adhesion to endothelial E-selectins [121]. Notably, these same mediators are also released following IS [80,122], suggesting that post-stroke inflammatory signaling may actively support metastatic arrest within cerebral vessels.
Following initial tethering, CTCs establish stable adhesion to the endothelium through stronger molecular interactions. Activated leukocyte cell adhesion molecule (ALCAM), expressed by both endothelial cells and tumor cells derived from breast and lung cancers, mediates homophilic binding that arrests CTCs within cerebral microvessels. In parallel, very late antigen-4 (VLA-4; integrin α4β1), expressed by breast cancer and melanoma cells, interacts with VCAM-1 in endothelial cells [60,61]. E-selectins further strengthen adhesion through binding to CD44 on tumor cells. Experimental disruption of these adhesion pathways markedly impairs brain metastasis, underscoring their essential role in tumor cell extravasation [60].
Once firmly adherent, tumor cells initiate transendothelial migration, which requires localized opening of the BBB. This process is facilitated by activation of matrix MMPs, which degrade TJ proteins, as well as by activation of the PI3K/AKT signaling pathway [60]. Stroke-induced BBB dysfunction lowers the threshold for these processes by weakening endothelial junctions and increasing paracellular permeability. An additional mechanism involves EMT, driven by TGF-β1 and specific microRNAs. During EMT, endothelial cells downregulate junctional proteins and acquire a mesenchymal phenotype characterized by expression of fibronectin, β1 integrin, and α-smooth muscle actin (α-SMA), thereby facilitating tumor transmigration.
After extravasation, tumor cells frequently adhere to the abluminal surface of cerebral capillaries, a process termed vascular co-option. This strategy provides immediate access to nutrients and supports subsequent angiogenic remodeling. Key mediators of vascular co-option include L1 cell adhesion molecule (L1CAM) and neuroserpin [123,124].
Astrocytes play a decisive role in determining whether extravasated tumor cells successfully establish metastatic lesions. Through extensive crosstalk with immune and vascular cells, astrocytes can generate a microenvironment that supports tumor growth. Hosonaga et al. demonstrated that astrocytic expression of STAT3 promotes brain metastasis of breast cancer in experimental models and human samples. STAT3-dependent upregulation of PD-L1 and VEGF-A suppresses CD8+ cytotoxic T-cell activity, thereby enabling tumor immune evasion [125]. Importantly, astrocytic STAT3 activation is also observed following CNS injury, including IS [126], further linking cerebrovascular insult to metastatic permissiveness.
Astrocytes additionally respond to tumor-derived extracellular vesicles containing regulatory microRNAs. For example, miR-181c alters astrocytic cytoskeletal organization, leading to increased BBB permeability, whereas miR-122 reprograms astrocytic glucose metabolism, preferentially redistributing nutrients to invading tumor cells. Additional astrocyte-mediated mechanisms mediated by astrocytes include deregulation of TJ protein expression and secretion of immunosuppressive and pro-tumorigenic cytokines [127].
Astrocytes may also exert anti-metastatic effects by releasing plasminogen activators, leading to plasmin activation. Plasmin cleaves Fas ligand (FasL) from astrocytes and L1CAM from tumor cells, thereby inducing tumor cell apoptosis and disrupting adhesion to the basal lamina [124]. However, endogenous plasmin signaling within the CNS can paradoxically promote metastasis. Tissue plasminogen activator activates platelet-derived growth factor-CC (PDGF-CC), enabling its interaction with PDGFR-α on perivascular astrocytes. This signaling cascade induces the expression and release of MMP-2 and MMP-9, which degrade TJ proteins and increase BBB permeability [128], thereby facilitating further tumor cell extravasation (Figure 3).
Figure 3.
Summary of mechanisms facilitating brain metastasis as a consequence of stroke.
The structurally and functionally altered vascular interface surrounding brain metastases and angiogenic vessels is known as the blood–tumor barrier (BTB). The BTB exhibits pronounced heterogeneity, characterized by pericyte dysfunction and displacement or loss of astrocytic endfeet, resulting in increased permeability [129]. Although enhanced BTB permeability may facilitate tumor progression by enabling continued tumor cell infiltration, it may also improve delivery of anticancer therapeutics to metastatic lesions [130]. Consequently, therapeutic modulation of the BBB–BTB continuum represents a critical challenge and opportunity in the management of brain metastases.
5. Correlation Between Strokes and Brain Cancers
Brain cancers are severe and debilitating conditions, and increasing evidence suggests that their development may share molecular and cellular mechanisms with cerebrovascular injury. Oxidative stress and hypoxia—hallmark features of IS—create a microenvironment conducive to tumor initiation and progression. Stroke-induced endothelial activation promotes expression of adhesion molecules that facilitate attachment of CTCs to the vascular wall, while concomitant BBB disruption lowers resistance to transendothelial migration into the CNS. In later stages, bidirectional crosstalk between tumor cells and astrocytes becomes critical for metastatic outgrowth, as glial cells can suppress antitumor immune responses and provide metabolic support for proliferating cancer cells. Despite these mechanistic overlaps, only a limited number of review articles have addressed the potential correlation between stroke and brain cancer [7], and none have focused specifically on the role of BBB dysfunction in this process.
Elucidating the relationship between stroke and brain cancer is complicated by shared pathophysiological pathways, including inflammation and hypoxia, as well as by temporal challenges. Clinical symptoms of malignancy may precede formal diagnosis by months or even years, making causal inference difficult. Consequently, much of the existing literature has focused on the more established association in which active malignancy increases the risk of stroke [12,15,16]. Brain tumors may precipitate IS through direct vascular compression by expanding tumor masses or through cancer-associated hypercoagulability driven by tumor cells or host immune responses. Moreover, stroke may occur as a complication of oncological treatments, including tumor resection, chemotherapy, and radiotherapy [16]. Brain metastases also represent a recognized risk factor for HS [15], potentially due to BBB disruption during metastatic extravasation.
Beyond molecular mechanisms, stroke-associated neurological deficits may indirectly influence cancer risk by altering lifestyle factors such as physical activity and diet, which have been implicated in cancer development [131]. However, in recent years, growing attention has been directed toward the reverse association—namely, whether cerebrovascular injury may increase the risk of subsequent brain cancer. A limited number of studies provide epidemiological evidence supporting this hypothesis.
A recent meta-analysis reported a hazard ratio of 2.75 for developing brain cancer following cerebrovascular disease [132], indicating a significant epidemiological association. Similarly, a meta-analysis by Rioux et al. demonstrated a higher cumulative incidence of cancer within one year after IS compared to the general population [13]. Notably, most malignancies were diagnosed several months after stroke, suggesting that in many cases, cancer may have been present but clinically undetected at the time of cerebrovascular injury. Long-term observational data further revealed that, ten years after stroke, the incidence of cancer was nearly doubled in patients aged 55 years or younger (17.3% vs. 9.5%), with a weaker but still significant association observed in older cohorts (29.4% vs. 24.9%) [14].
More direct evidence linking stroke with brain cancer development was provided by Chen et al., who analyzed a nationwide Taiwanese cohort of GBM patients [8]. They found that individuals with a prior stroke exhibited a significantly higher adjusted hazard ratio (3.09) for developing brain cancer compared to the general population. Histological analysis revealed strong HIF-1α expression in tumor tissues from stroke-exposed patients, whereas this marker was largely absent in non-exposed controls [8], implicating hypoxia-driven signaling in gliomagenesis. Complementary bioinformatic analysis by Islam et al. identified 57 genes shared between IS and glioblastoma, including CXCR4, a key regulator of brain metastasis [10,133,134]. In contrast, a Mendelian randomization study examining genetic predictors of IS and glioblastoma did not identify a significant causal association [11], suggesting that shared molecular pathways, rather than inherited genetic predisposition, may underlie the observed correlation.
Clinical case reports further support a potential link between stroke and subsequent brain malignancy. Gwak et al. described a 48-year-old male with renal cell carcinoma who developed an acute IS associated with cancer-related coagulopathy, followed by the appearance of brain metastasis eight months later within the infarcted region [135]. Similarly, another report documented brain metastasis from pulmonary adenocarcinoma arising five months after an ischemic stroke caused by occlusion of the middle cerebral artery, with both lesions localized to the same brain territory [136]. In both cases, the authors proposed stroke-mediated BBB disruption as a key etiological factor. Additional hypotheses include tumor exploitation of post-ischemic angiogenesis and creation of a permissive “soil” within infarcted tissue.
Notably, this phenomenon does not appear to be limited to IS. A case study described a 22-year-old female who developed HS in the left frontotemporoparietal region and was diagnosed 16 years later with malignant melanoma metastasis localized to the same area [137]. These observations suggest that brain metastasis may occur independently of stroke subtype, etiology, or latency period.
While individual case reports provide compelling proof-of-concept evidence, their inherent limitations necessitate validation in larger patient cohorts. To date, only one retrospective study has systematically examined this association. In a cohort of 307 patients with non-small cell lung cancer, cerebral infarction emerged as an independent risk factor for brain metastasis (odds ratio 3.303; 95% confidence interval 1.437–7.593; p = 0.005) [138]. These findings underscore the need for prospective, hypothesis-driven studies specifically designed to capture temporal dynamics, stroke characteristics, and BBB integrity.
In addition to secondary brain tumors, several reports describe glioblastoma developing within regions previously affected by stroke. We identified three cases of GBM arising after ischemic infarction [139,140,141] and one case following HS [142]. Tumor diagnosis occurred between seven months and three years after the cerebrovascular event, with no radiological evidence of pre-existing malignancy. Collectively, these observations support the concept that ischemia-induced tissue damage, revascularization, and persistent BBB remodeling may create a permissive niche for malignant transformation.
Based on the available evidence, female sex and age between 40 and 60 years appear to represent potential risk modifiers for brain cancer development after stroke [8]. Identification of such subgroups may have clinical relevance, as earlier diagnosis of brain tumors is associated with improved prognosis [143]. However, larger and more diverse cohorts are required to validate these observations and identify additional predisposing factors.
From a translational perspective, therapeutic strategies aimed at preserving BBB integrity may offer dual benefits by mitigating neurodegenerative sequelae of stroke while potentially reducing susceptibility to brain cancer. Several candidate approaches have been proposed based on preclinical evidence, including borneol [144], c-Jun N-terminal kinase (JNK) inhibitors [57], modulation of atractylon-mediated sirtuin 3 (SIRT3) signaling [145,146,147], and Z-ligustilide (Z-Lig). Borneol exhibits anti-inflammatory properties that may attenuate stroke-induced MMP-9 activation and reduce the immunosuppressive potential of gliomas [144]. Similarly, JNK inhibition has been shown to preserve BBB integrity in experimental models of both stroke and cancer [57]. Modulation of SIRT3 signaling stabilizes the BBB through inhibition of the HIF-1α/VEGF axis while simultaneously sensitizing glioblastoma cells to ferroptosis and autophagy, resulting in reduced tumor growth in preclinical studies [145,146,147]. Z-ligustilide, an active compound derived from Ligusticum chuanxiong, reduces neuroinflammation after stroke and improves temozolomide pharmacokinetics in experimental glioblastoma models. Although its precise mechanisms remain incompletely defined, Z-Lig has been shown to modulate hypoxia signaling and downregulate P-glycoprotein, claudin-5, and occludin expression, thereby facilitating drug penetration across the BBB [148,149]. Importantly, the potential adverse consequences of BBB modulation, including excessive barrier permeability, require careful evaluation. At present, all therapeutic strategies discussed remain at the preclinical stage, with supporting evidence derived exclusively from in vitro and animal studies [57,144,145,146,147,148,149]. Accordingly, any potential clinical benefit should be interpreted as prospective rather than established.
Beyond therapeutic approaches, emerging diagnostic strategies aim to detect BBB alterations at early stages. Dynamic contrast-enhanced magnetic resonance imaging (DCE-MRI) is currently a standard technique for in vivo assessment of BBB permeability [150]. Immuno-MRI enables visualization of endothelial activation and adhesion molecule expression associated with neuroinflammation [40]. Other approaches, such as total-body positron emission tomography (PET), allow functional monitoring of BBB permeability across different particle sizes [151]. In parallel, circulating biomarkers of NVU injury—including PDGFRβ, HIF-1α, TNF-α, and ZO-1—can be quantified in peripheral blood, offering promising avenues for early diagnosis and longitudinal monitoring [39,107].
Despite growing mechanistic and epidemiological interest in the relationship between cerebrovascular injury, BBB dysfunction, and brain cancer, this field faces substantial inherent limitations. Stroke is a life-threatening condition in which clinical priorities are necessarily focused on acute, life-saving interventions rather than long-term surveillance or prophylaxis of secondary complications. In addition, the co-occurrence of stroke and brain cancer appears to be relatively rare, as reflected by the limited number of reported clinical cases. Together, these factors constrain both the quality and quantity of available clinical data and complicate the design of systematic, hypothesis-driven studies addressing the stroke–BBB–brain cancer axis.
Moreover, the novelty of current research efforts—largely centered on molecular and cellular mechanisms linking stroke and cancer—further limits the availability of robust clinical evidence. In this context, careful literature selection and integrative analysis are essential for advancing the field, as emphasized by De Simone et al. [152]. Accordingly, given the scarcity of directly relevant clinical studies available as of 2026, the selection of sources included in this review was adapted to reflect the emerging and exploratory nature of this research area.
It is also important to acknowledge several confounding factors that may influence the reported association between stroke and subsequent brain cancer. Both conditions share multiple vascular and lifestyle-related risk factors, including hypertension, diabetes, active smoking, and excessive alcohol consumption, which may partially account for observed correlations [153]. In addition, stroke patients typically receive more frequent and comprehensive medical follow-up, including repeated neuroimaging, which increases the likelihood of detecting developing or previously unrecognized brain tumors compared to the general population, thereby introducing surveillance bias. Furthermore, the presence of occult or asymptomatic brain tumors at the time of the cerebrovascular event cannot be excluded, raising the possibility of reverse causation in a subset of epidemiological analyses. These limitations underscore the need for well-designed, unbiased cohort studies—particularly those comparing the incidence of brain tumors with other cancer types in stroke survivors—to more accurately define the temporal relationship and mitigate detection bias. Nevertheless, the evidence summarized herein highlights BBB dysfunction as a biologically plausible mechanistic link between cerebrovascular injury and brain malignancy. Targeting BBB integrity may therefore represent a promising strategy not only for understanding these rare comorbidities but also for improving outcomes in stroke and brain cancer as independent disease entities.
6. Conclusions
The body of evidence reviewed here supports the concept that disruption of the BBB after stroke may contribute to the subsequent development of brain tumors. Epidemiological studies consistently indicate that cerebrovascular events constitute a significant risk factor for brain cancer, a relationship further reinforced by multiple clinical case reports documenting tumor emergence within previously infarcted or hemorrhagic brain regions. Although precise causal mechanisms remain incompletely defined, converging data implicate hypoxia, oxidative stress, and neuroinflammation as central drivers of post-stroke microenvironmental remodeling.
A key contribution of this review is the integration of BBB dysfunction into the stroke–brain cancer axis as a unifying mechanistic framework, rather than viewing BBB alterations solely as secondary consequences of cerebrovascular injury or as barriers to therapeutic delivery. These processes promote degradation of endothelial tight junctions, endothelial activation, and increased expression of adhesion molecules, collectively facilitating adhesion, extravasation, and survival of circulating tumor cells within the central nervous system. In later stages of stroke recovery, growth factor signaling, angiogenesis, metabolic reprogramming, and immune suppression may further support tumor initiation and progression by creating a permissive niche for malignant transformation and metastatic colonization.
Importantly, while current evidence supports strong mechanistic plausibility linking stroke-induced BBB dysfunction with brain tumor development, this relationship should be interpreted as largely associative and hypothesis-generating rather than causally definitive. Based on the data summarized herein, several testable hypotheses emerge, including the existence of a defined temporal window of increased oncological vulnerability following stroke, the prognostic value of persistent BBB permeability changes, and the contribution of specific neuroinflammatory signaling pathways to tumor-permissive BBB remodeling.
Accordingly, future research should prioritize longitudinal, prospective clinical studies that correlate temporal changes in BBB permeability with brain tumor incidence and metastatic burden following cerebrovascular injury. Mechanistically informed in vitro and in vivo models are also needed to dissect shared molecular signatures of BBB disruption, stroke recovery, and tumor progression. Furthermore, interventional approaches targeting BBB-stabilizing and anti-inflammatory pathways, including modulation of NF-κB signaling, warrant systematic evaluation as potential strategies to reduce secondary CNS malignancies or metastatic seeding after stroke.
From a clinical perspective, these findings suggest that enhanced vigilance regarding BBB integrity may be particularly relevant for stroke survivors with a history of malignancies characterized by a high propensity for CNS metastasis, such as lung cancer, breast cancer, and melanoma. In this context, BBB integrity may serve not only as a mechanistic marker but also as a risk stratification tool for identifying high-risk patient subgroups.
There are also diagnostic approaches with potential relevance for clinical translation. Plasma circulating tumor DNA represents a viable diagnostic tool and an alternative to cerebrospinal fluid analysis for detecting brain metastases, offering a minimally invasive option for high-risk patients [154]. In parallel, dynamic susceptibility contrast MRI enables mapping of BBB leakage to identify tissue at risk of infarction and potential metastatic niches [155].
Collectively, these insights position the BBB not only as a passive victim of cerebrovascular injury but as an active, dynamic, and clinically actionable determinant of long-term neurological and oncological outcomes, highlighting BBB integrity as a promising and conceptually unifying target for future diagnostic, prognostic, and therapeutic strategies at the intersection of stroke and brain cancer.
Author Contributions
Conceptualization, S.K., J.Ś., A.B. and R.Z.; writing—original draft preparation, S.K., M.P., W.J.N., W.J. and A.B.; writing—review and editing, A.B., K.R. and R.Z.; visualization, S.K. and A.B.; supervision, A.B. and R.Z.; project administration, R.Z.; funding acquisition, R.Z. All authors have read and agreed to the published version of the manuscript.
Funding
This research was founded by NCN as part of the “Blood–brain barrier: A 3D cell model and its functionality assessed by a multimodal molecular platform.” project No. 2021/41/B/ST4/02000 OPUS21.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
The authors would like to acknowledge Kamilla Małek from Department of Chemistry, Jagiellonian University for her contribution as principal investigator, including coordination of project activities.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ABC | ATP binding cassette |
| AJ | adherent junction |
| Akt/NF-κB | kinase Akt mediated nuclear factor κB signaling pathway |
| ALCAM | activated leukocyte cell adhesion molecule |
| AMPK | AMP-activated protein kinase |
| Ang-1 | angiopoietin-1 |
| Ang-2 | angiopoietin-2 |
| AQP4 | aquaporin 4 |
| BBB | blood–brain barrier |
| BCRP | breast cancer resistance protein |
| BDNF | brain-derived neurotrophic factor |
| BNIP3 | BCL2/adenovirus E1B 19 kDa—interacting protein 3 |
| BTB | blood–tumor barrier |
| CCL | C-C motif chemokine ligand |
| CDK | cyclin-dependent kinase |
| CNS | central nervous system |
| COX-2 | cyclooxygenase-2 |
| CSF | cerebrospinal fluid |
| CTC | circulating tumor cell |
| CXCL1 | C-X-C motif chemokine ligand 1 |
| DCE-MRI | dynamic contrast enhanced magnetic resonance imaging |
| DNA-PK | PK-DNA dependent protein kinase |
| EGFR | epidermal growth factor receptor |
| EMT | epithelial to mesenchymal transition |
| EndMT | endothelial-to-mesenchymal transition |
| EPO | erythropoietin |
| GAL3ST1 | galactosylceramide sulfotransferase 1 |
| GBM | glioblastoma multiforme |
| GLUT1 | glucose transporter 1 |
| GPx | glutathione peroxidase |
| HIF-1 | Hypoxia-inducible factor 1 |
| HIG2 | hypoxia-inducible gene 2 |
| HS | hemorrhagic stroke |
| I/R | ischemia–reperfusion |
| ICAM-1 | intercellular adhesion molecule 1 |
| IFP35 | interferon-induced protein 35 |
| IL | interleukin |
| IP-10 | interferon-γ–inducible protein-10 |
| IS | ischemic stroke |
| JAM | junctional adhesion molecule |
| JNK | c-Jun N-terminal kinase |
| L1CAM | L1 cell adhesion molecule |
| MAPK | mitogen-activated protein kinase |
| MCP-1 | monocyte chemoattractant protein-1 |
| MDSC | myeloid-derived suppressor cell |
| MIP-1α | Macrophage Inflammatory Protein 1α |
| MKK4 | mitogen-activated protein kinase 4 |
| MLCK | myosin light-chain kinase |
| MMP | matrix metalloproteinase |
| MRP | multidrug resistance associated protein |
| mTOR | mammalian target of rapamycin |
| NADPH | nicotinamide adenine dinucleotide phosphate |
| NF-κB | nuclear factor κB |
| NGF | nerve growth factor |
| NK | natural killers |
| NRF2 | nuclear factor erythroid 2–related factor 2 |
| NSCLC | non-small cell lung cancer |
| NT-3 | neurotrophin-3 |
| NVU | neurovascular unit |
| OPC | oligodendrocyte precursor cell |
| PAR | protease-activated receptor |
| PARP | poly(ADP-ribose) polymerase |
| PAs | plasminogen activators |
| PDGF | platelet-derived growth factor |
| PDGF-CC | platelet-derived growth factor-CC |
| PDGFRβ | platelet-derived growth factor receptor β |
| PD-L1 | programmed death ligand 1 |
| PET | positron emission tomography |
| P-gp | P-glycoprotein |
| PI3K | phosphatidylinositol 3-kinase |
| PKC | protein kinase C |
| PLC-γ | phospholipase C gamma |
| PTEN | phosphatase and tensin homolog |
| PTN | pericytes release pleiotrophin |
| RNS | reactive nitrogen species |
| ROS | reactive oxygen species |
| SIRT3 | atractylon-mediated sirtuin 3 |
| SOD | superoxide dismutase |
| STAT3 | signal transducer and activator of transcription 3 |
| TGF-β | transforming growth factor β |
| TIAs | transient ischemic attacks |
| TJs | tight junctions |
| TNF-α | tumor necrosis factor α |
| TP53 | tumour protein p53 |
| Treg | regulatory T cell |
| VCAM-1 | vascular cell adhesion molecule 1 |
| VEGF | vascular endothelial growth factor |
| VEGFR2 | vascular endothelial growth factor receptor 2 |
| VLA-4 | very late antigen-4 |
| Z-Lig | Z-ligustilide |
| ZO | zona occludens |
| α-SMA | α-smooth muscle actin |
References
- Feigin, V.L.; Brainin, M.; Norrving, B.; Martins, S.O.; Pandian, J.; Lindsay, P.; Grupper, M.F.; Rautalin, I. World Stroke Organization: Global Stroke Fact Sheet 2025. Int. J. Stroke 2025, 20, 132–144. [Google Scholar] [CrossRef] [Scilit]
- Ahmed, Z.; Chaudhary, F.; Agrawal, D.K. Epidemiology, Pathophysiology, and Current Treatment Strategies in Stroke. Cardiol. Cardiovasc. Med. 2024, 8, 389–404. [Google Scholar] [CrossRef] [Scilit]
- Price, M.; Ballard, C.; Benedetti, J.; Neff, C.; Cioffi, G.; Waite, K.A.; Kruchko, C.; Barnholtz-Sloan, J.S.; Ostrom, Q.T. CBTRUS Statistical Report: Primary Brain and Other Central Nervous System Tumors Diagnosed in the United States in 2017–2021. Neuro-oncology 2024, 26, vi1–vi85. [Google Scholar] [CrossRef] [Scilit]
- van Tellingen, O.; Yetkin-Arik, B.; de Gooijer, M.C.; Wesseling, P.; Wurdinger, T.; de Vries, H.E. Overcoming the Blood-Brain Tumor Barrier for Effective Glioblastoma Treatment. Drug Resist. Updat. Rev. Comment. Antimicrob. Anticancer Chemother. 2015, 19, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Sadowski, K.; Jażdżewska, A.; Kozłowski, J.; Zacny, A.; Lorenc, T.; Olejarz, W. Revolutionizing Glioblastoma Treatment: A Comprehensive Overview of Modern Therapeutic Approaches. Int. J. Mol. Sci. 2024, 25, 5774. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, J.; Gu, L.; Du, F.; Li, C.; Zhang, F.; Zhang, X.; Pang, J.; Xie, B.; Wang, X.; Peng, J.; et al. The Global, Regional, and National Brain and CNS Cancers Burden and Trends from 1990 to 2021. Sci. Rep. 2025, 15, 19228. [Google Scholar] [CrossRef] [Scilit]
- Ghosh, M.K.; Chakraborty, D.; Sarkar, S.; Bhowmik, A.; Basu, M. The Interrelationship between Cerebral Ischemic Stroke and Glioma: A Comprehensive Study of Recent Reports. Signal Transduct. Target. Ther. 2019, 4, 42. [Google Scholar] [CrossRef] [Scilit]
- Chen, C.-W.; Cheng, T.-J.; Ho, C.-H.; Wang, J.-J.; Weng, S.-F.; Hou, Y.-C.; Cheng, H.-C.; Chio, C.-C.; Shan, Y.-S.; Chang, W.-T. Increased Risk of Brain Cancer Incidence in Stroke Patients: A Clinical Case Series, Population-Based and Longitudinal Follow-up Study. Oncotarget 2017, 8, 108989–108999. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hao, Z.; Guan, W.; Wei, W.; Li, M.; Xiao, Z.; Sun, Q.; Pan, Y.; Xin, W. Unlocking the Therapeutic Potential of Tumor-Derived EVs in Ischemia-Reperfusion: A Breakthrough Perspective from Glioma and Stroke. J. Neuroinflamm. 2025, 22, 84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Islam, M.K.; Islam, M.R.; Rahman, M.H.; Islam, M.Z.; Amin, M.A.; Ahmed, K.R.; Rahman, M.A.; Moni, M.A.; Kim, B. Bioinformatics Strategies to Identify Shared Molecular Biomarkers That Link Ischemic Stroke and Moyamoya Disease with Glioblastoma. Pharmaceutics 2022, 14, 1573. [Google Scholar] [CrossRef] [Scilit]
- Liu, H.; Yang, Y.; Wei, Z.; Liu, N. Causality between Ischemic Stroke and Glioblastoma: Bidirectional Mendelian Randomization Analysis. Medicine 2025, 104, e42697. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Menounos, S.; Shen, H.; Tipirneni, S.; Bhaskar, S.M.M. Decoding the Nexus: Cellular and Molecular Mechanisms Linking Stroke and Neurotoxic Microenvironments in Brain Cancer Patients. Biomolecules 2024, 14, 1507. [Google Scholar] [CrossRef] [Scilit]
- Rioux, B.; Touma, L.; Nehme, A.; Gore, G.; Keezer, M.R.; Gioia, L.C. Frequency and Predictors of Occult Cancer in Ischemic Stroke: A Systematic Review and Meta-Analysis. Int. J. Stroke 2021, 16, 12–19. [Google Scholar] [CrossRef] [Scilit]
- Tanislav, C.; Adarkwah, C.C.; Jakob, L.; Kostev, K. Increased Risk for Cancer after Stroke at a Young Age: Etiological Relevance or Incidental Finding? J. Cancer Res. Clin. Oncol. 2019, 145, 3047–3054. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Woock, M.; Martinez-Majander, N.; Seiffge, D.J.; Selvik, H.A.; Nordanstig, A.; Redfors, P.; Lindgren, E.; Sanchez van Kammen, M.; Rentzos, A.; Coutinho, J.M.; et al. Cancer and Stroke: Commonly Encountered by Clinicians, but Little Evidence to Guide Clinical Approach. Ther. Adv. Neurol. Disord. 2022, 15, 17562864221106362. [Google Scholar] [CrossRef] [Scilit]
- Zuber, M. Stroke and Cancer. Rev. Neurol. 2023, 179, 417–424. [Google Scholar] [CrossRef] [Scilit]
- Menaceur, C.; Gosselet, F.; Fenart, L.; Saint-Pol, J.; Menaceur, C.; Gosselet, F.; Fenart, L.; Saint-Pol, J. The Blood–Brain Barrier, an Evolving Concept Based on Technological Advances and Cell–Cell Communications. Cells 2021, 11, 133. [Google Scholar] [CrossRef] [Scilit]
- Peters, J.J.; Teng, C.; Peng, K.; Li, X. Deciphering the Blood–Brain Barrier Paradox in Brain Metastasis Development and Therapy. Cancers 2025, 17, 298. [Google Scholar] [CrossRef] [Scilit]
- Lochhead, J.J.; Yang, J.; Ronaldson, P.T.; Davis, T.P. Structure, Function, and Regulation of the Blood-Brain Barrier Tight Junction in Central Nervous System Disorders. Front. Physiol. 2020, 11, 914. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almutairi, M.M.A.; Gong, C.; Xu, Y.G.; Chang, Y.; Shi, H. Factors Controlling Permeability of the Blood–Brain Barrier. Cell. Mol. Life Sci. 2016, 73, 57–77. [Google Scholar] [CrossRef] [Scilit]
- Kadry, H.; Noorani, B.; Cucullo, L. A Blood-Brain Barrier Overview on Structure, Function, Impairment, and Biomarkers of Integrity. Fluids Barriers CNS 2020, 17, 69. [Google Scholar] [CrossRef] [Scilit]
- Armulik, A.; Genové, G.; Mäe, M.; Nisancioglu, M.H.; Wallgard, E.; Niaudet, C.; He, L.; Norlin, J.; Lindblom, P.; Strittmatter, K.; et al. Pericytes Regulate the Blood–Brain Barrier. Nature 2010, 468, 557–561. [Google Scholar] [CrossRef] [Scilit]
- Medina-Flores, F.; Hurtado-Alvarado, G.; Deli, M.A.; Gómez-González, B. The Active Role of Pericytes During Neuroinflammation in the Adult Brain. Cell. Mol. Neurobiol. 2023, 43, 525–541. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, Z.; Nelson, A.R.; Betsholtz, C.; Zlokovic, B.V. Establishment and Dysfunction of the Blood-Brain Barrier. Cell 2015, 163, 1064–1078. [Google Scholar] [CrossRef] [Scilit]
- Takata, F.; Nakagawa, S.; Matsumoto, J.; Dohgu, S. Blood-Brain Barrier Dysfunction Amplifies the Development of Neuroinflammation: Understanding of Cellular Events in Brain Microvascular Endothelial Cells for Prevention and Treatment of BBB Dysfunction. Front. Cell. Neurosci. 2021, 15, 661838. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Shen, Y.; Yu, X.; Gu, J.; Zhang, X.; Zhou, B.; Sun, Y.; Xu, C.; Qian, S. Role of NADPH Oxidase-Induced Hypoxia-Induced Factor-1α Increase in Blood-Brain Barrier Disruption after 2-Hour Focal Ischemic Stroke in Rat. Neural Plast. 2021, 2021, 9928232. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daneman, R.; Prat, A. The Blood–Brain Barrier. Cold Spring Harb. Perspect. Biol. 2015, 7, a020412. [Google Scholar] [CrossRef] [Scilit]
- McConnell, H.L.; Mishra, A. Cells of the Blood-Brain Barrier: An Overview of the Neurovascular Unit in Health and Disease. Methods Mol. Biol. Clifton NJ 2022, 2492, 3–24. [Google Scholar] [CrossRef] [Scilit]
- McConnell, H.L.; Li, Z.; Woltjer, R.L.; Mishra, A. Astrocyte Dysfunction and Neurovascular Impairment in Neurological Disorders: Correlation or Causation? Neurochem. Int. 2019, 128, 70–84. [Google Scholar] [CrossRef] [Scilit]
- Gao, H.; Chen, H.; Cui, G.-Y.; Hu, J.-X. Damage Mechanism and Therapy Progress of the Blood-Brain Barrier after Ischemic Stroke. Cell Biosci. 2023, 13, 196. [Google Scholar] [CrossRef] [Scilit]
- Abdullahi, W.; Tripathi, D.; Ronaldson, P.T. Blood-Brain Barrier Dysfunction in Ischemic Stroke: Targeting Tight Junctions and Transporters for Vascular Protection. Am. J. Physiol.-Cell Physiol. 2018, 315, C343–C356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shekhar, S.; Cunningham, M.W.; Pabbidi, M.R.; Wang, S.; Booz, G.W.; Fan, F. Targeting Vascular Inflammation in Ischemic Stroke: Recent Developments on Novel Immunomodulatory Approaches. Eur. J. Pharmacol. 2018, 833, 531–544. [Google Scholar] [CrossRef] [Scilit]
- Veeravalli, K.K. Implications of MMP-12 in the Pathophysiology of Ischaemic Stroke. Stroke Vasc. Neurol. 2024, 9, 97–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lochhead, J.J.; Ronaldson, P.T.; Davis, T.P. The Role of Oxidative Stress in Blood-Brain Barrier Disruption during Ischemic Stroke: Antioxidants in Clinical Trials. Biochem. Pharmacol. 2024, 228, 116186. [Google Scholar] [CrossRef] [Scilit]
- Dang, Q.B.; Lapergue, B.; Tran-Dinh, A.; Diallo, D.; Moreno, J.-A.; Mazighi, M.; Romero, I.A.; Weksler, B.; Michel, J.-B.; Amarenco, P.; et al. High-Density Lipoproteins Limit Neutrophil-Induced Damage to the Blood–Brain Barrier in Vitro. J. Cereb. Blood Flow Metab. 2013, 33, 575–582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ye, F.; Garton, H.J.L.; Hua, Y.; Keep, R.F.; Xi, G. The Role of Thrombin in Brain Injury After Hemorrhagic and Ischemic Stroke. Transl. Stroke Res. 2021, 12, 496–511. [Google Scholar] [CrossRef] [Scilit]
- Niego, B.; Medcalf, R.L. Plasmin-Dependent Modulation of the Blood-Brain Barrier: A Major Consideration during tPA-Induced Thrombolysis? J. Cereb. Blood Flow Metab. Off. J. Int. Soc. Cereb. Blood Flow Metab. 2014, 34, 1283–1296. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Chen, G. CNS-Peripheral Immune Interactions in Hemorrhagic Stroke. J. Cereb. Blood Flow Metab. 2023, 43, 185–197. [Google Scholar] [CrossRef] [Scilit]
- French, S.; Arias, J.; Bolakale-Rufai, I.; Zahra, S.; Khakwani, K.Z.R.; Bedrick, E.J.; Serrano, G.E.; Beach, T.G.; Reiman, E.; Weinkauf, C. Serum Detection of Blood Brain Barrier Injury in Subjects with a History of Stroke and Transient Ischemic Attack. JVS-Vasc. Sci. 2024, 5, 100206. [Google Scholar] [CrossRef] [Scilit]
- Fournier, A.P.; Morvan, M.I.; de Lizarrondo, S.M.; Gauberti, M. Immuno-MRI for Stroke Diagnosis and Prognosis. Neuroscience 2024, 550, 53–61. [Google Scholar] [CrossRef] [Scilit]
- Sipos, E.; Chen, L.; András, I.E.; Wrobel, J.; Zhang, B.; Pu, H.; Park, M.; Eum, S.Y.; Toborek, M. Proinflammatory Adhesion Molecules Facilitate Polychlorinated Biphenyl–Mediated Enhancement of Brain Metastasis Formation. Toxicol. Sci. 2012, 126, 362–371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Török, O.; Schreiner, B.; Schaffenrath, J.; Tsai, H.-C.; Maheshwari, U.; Stifter, S.A.; Welsh, C.; Amorim, A.; Sridhar, S.; Utz, S.G.; et al. Pericytes Regulate Vascular Immune Homeostasis in the CNS. Proc. Natl. Acad. Sci. USA 2021, 118, e2016587118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soto, M.S.; Serres, S.; Anthony, D.C.; Sibson, N.R. Functional Role of Endothelial Adhesion Molecules in the Early Stages of Brain Metastasis. Neuro-oncology 2014, 16, 540–551. [Google Scholar] [CrossRef] [Scilit]
- Taftaf, R.; Liu, X.; Singh, S.; Jia, Y.; Dashzeveg, N.K.; Hoffmann, A.D.; El-Shennawy, L.; Ramos, E.K.; Adorno-Cruz, V.; Schuster, E.J.; et al. ICAM1 Initiates CTC Cluster Formation and Trans-Endothelial Migration in Lung Metastasis of Breast Cancer. Nat. Commun. 2021, 12, 4867. [Google Scholar] [CrossRef] [Scilit]
- Sies, H. Oxidative Stress: A Concept in Redox Biology and Medicine. Redox Biol. 2015, 4, 180–183. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lehner, C.; Gehwolf, R.; Tempfer, H.; Krizbai, I.; Hennig, B.; Bauer, H.-C.; Bauer, H. Oxidative Stress and Blood–Brain Barrier Dysfunction Under Particular Consideration of Matrix Metalloproteinases. Antioxid. Redox Signal. 2011, 15, 1305–1323. [Google Scholar] [CrossRef] [Scilit]
- Agrawal, K.; Asthana, S.; Kumar, D. Role of Oxidative Stress in Metabolic Reprogramming of Brain Cancer. Cancers 2023, 15, 4920. [Google Scholar] [CrossRef] [Scilit]
- Yun, H.J.; Li, M.; Guo, D.; Jeon, S.M.; Park, S.H.; Lim, J.S.; Lee, S.B.; Liu, R.; Du, L.; Kim, S.-H.; et al. AMPK-HIF-1α Signaling Enhances Glucose-Derived de Novo Serine Biosynthesis to Promote Glioblastoma Growth. J. Exp. Clin. Cancer Res. CR 2023, 42, 340. [Google Scholar] [CrossRef] [Scilit]
- Ding, Z.-B.; Song, L.-J.; Wang, Q.; Kumar, G.; Yan, Y.-Q.; Ma, C.-G. Astrocytes: A Double-Edged Sword in Neurodegenerative Diseases. Neural Regen. Res. 2021, 16, 1702–1710. [Google Scholar] [CrossRef] [Scilit]
- Geng, X.; Geng, Z.; Li, H.; Zhang, Y.; Li, J.; Chang, H. Over-expression of TFB2M Facilitates Cell Growth and Metastasis via Activating ROS-Akt-NF-κB Signalling in Hepatocellular Carcinoma. Liver Int. 2020, 40, 1756–1769. [Google Scholar] [CrossRef] [Scilit]
- Min, W.L.; Wang, B.F.; Liang, B.B.; Zhang, L.; Pan, J.Y.; Huang, Y.; Zhao, Y.; Lin, S.; Zhao, Y.H.; Zhang, S.Q.; et al. A ROS/Akt/NF-κB Signaling Cascade Mediates Epidermal Growth Factor-Induced Epithelial-Mesenchymal Transition and Invasion in Human Breast Cancer Cells. World J. Oncol. 2022, 13, 289–298. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.; Jung, U.J.; Kim, S.R. Role of Oxidative Stress in Blood–Brain Barrier Disruption and Neurodegenerative Diseases. Antioxidants 2024, 13, 1462. [Google Scholar] [CrossRef] [Scilit]
- Esteban-Román, N.F.; Taddei, E.; Castro-Velázquez, E.; Villafuentes-Vidal, L.; Velez-Herrera, A.; Rubio-Osornio, M.; Rubio, C. Redox-Regulated Pathways in Glioblastoma Stem-like Cells: Mechanistic Insights and Therapeutic Implications. Brain Sci. 2025, 15, 884. [Google Scholar] [CrossRef] [Scilit]
- Jhanwar-Uniyal, M.; Dominguez, J.F.; Mohan, A.L.; Tobias, M.E.; Gandhi, C.D. Disentangling the Signaling Pathways of mTOR Complexes, mTORC1 and mTORC2, as a Therapeutic Target in Glioblastoma. Adv. Biol. Regul. 2022, 83, 100854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pudełek, M.; Król, K.; Catapano, J.; Wróbel, T.; Czyż, J.; Ryszawy, D. Epidermal Growth Factor (EGF) Augments the Invasive Potential of Human Glioblastoma Multiforme Cells via the Activation of Collaborative EGFR/ROS-Dependent Signaling. Int. J. Mol. Sci. 2020, 21, 3605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saurty-Seerunghen, M.S.; Daubon, T.; Bellenger, L.; Delaunay, V.; Castro, G.; Guyon, J.; Rezk, A.; Fabrega, S.; Idbaih, A.; Almairac, F.; et al. Glioblastoma Cell Motility Depends on Enhanced Oxidative Stress Coupled with Mobilization of a Sulfurtransferase. Cell Death Dis. 2022, 13, 913. [Google Scholar] [CrossRef] [Scilit]
- Plotnikov, M.B.; Anishchenko, A.M.; Khlebnikov, A.I.; Schepetkin, I.A. Regulation of Blood–Brain Barrier Permeability via JNK Signaling Pathway: Mechanisms and Potential Therapeutic Strategies for Ischemic Stroke, Alzheimer’s Disease and Brain Tumors. Molecules 2025, 30, 2353. [Google Scholar] [CrossRef] [Scilit]
- Xia, S.; Duan, W.; Xu, M.; Li, M.; Tang, M.; Wei, S.; Lin, M.; Li, E.; Liu, W.; Wang, Q. Mesothelin Promotes Brain Metastasis of Non-Small Cell Lung Cancer by Activating MET. J. Exp. Clin. Cancer Res. CR 2024, 43, 103. [Google Scholar] [CrossRef] [Scilit]
- Liang, Z.; Zhao, S.; Liu, Y.; Cheng, C. The Promise of Mitochondria in the Treatment of Glioblastoma: A Brief Review. Discov. Oncol. 2025, 16, 142. [Google Scholar] [CrossRef] [Scilit]
- Alsabbagh, R.; Ahmed, M.; Alqudah, M.A.Y.; Hamoudi, R.; Harati, R. Insights into the Molecular Mechanisms Mediating Extravasation in Brain Metastasis of Breast Cancer, Melanoma, and Lung Cancer. Cancers 2023, 15, 2258. [Google Scholar] [CrossRef] [Scilit]
- Saltarin, F.; Wegmüller, A.; Bejarano, L.; Ildiz, E.S.; Zwicky, P.; Vianin, A.; Spadin, F.; Soukup, K.; Wischnewski, V.; Engelhardt, B.; et al. Compromised Blood-Brain Barrier Junctions Enhance Melanoma Cell Intercalation and Extravasation. Cancers 2023, 15, 5071. [Google Scholar] [CrossRef] [Scilit]
- Zeng, Y.; Lu, X.; Wang, Y.; He, J.; Cao, H.; Zhang, L.; Cheng, L. Recent Status and Trends Regarding Oxidative Stress in Gliomas (2013–2025): A Systematic Review and Bibliometric Analysis. Front. Oncol. 2025, 15, 1586515. [Google Scholar] [CrossRef] [Scilit]
- Tang, T.; Jia, Y.; Liang, H.; Han, Y.; Cong, Z.; Wang, H.; Ji, X. Knockdown of Nrf2 Radiosensitizes Glioma Cells by Inducing Redox Stress and Apoptosis in Hypoxia. Transl. Cancer Res. 2022, 11, 4105–4116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mao, X.W.; Pecaut, M.J.; Stanbouly, S.; Nelson, G. Oxidative Stress, Neuroinflammation, and the Blood-Brain Barrier Biomarkers on the Brain Response to Spaceflight. Life Sci. Space Res. 2024, 43, 22–28. [Google Scholar] [CrossRef] [Scilit]
- Firdous, S.M.; Khan, S.A.; Maity, A. Oxidative Stress-Mediated Neuroinflammation in Alzheimer’s Disease. Naunyn. Schmiedebergs Arch. Pharmacol. 2024, 397, 8189–8209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beltran-Velasco, A.I.; Clemente-Suárez, V.J. Impact of Peripheral Inflammation on Blood–Brain Barrier Dysfunction and Its Role in Neurodegenerative Diseases. Int. J. Mol. Sci. 2025, 26, 2440. [Google Scholar] [CrossRef] [Scilit]
- Kovac, A.; Erickson, M.A.; Banks, W.A. Brain Microvascular Pericytes Are Immunoactive in Culture: Cytokine, Chemokine, Nitric Oxide, and LRP-1 Expression in Response to Lipopolysaccharide. J. Neuroinflamm. 2011, 8, 139. [Google Scholar] [CrossRef] [Scilit]
- Liu, C.; Guo, Y.; Deng, S.; Zhou, S.; Wu, S.; Chen, T.; Shi, X.; Mamtilahun, M.; Xu, T.; Liu, Z.; et al. Hemorrhagic Stroke-Induced Subtype of Inflammatory Reactive Astrocytes Disrupts Blood-Brain Barrier. J. Cereb. Blood Flow Metab. 2024, 44, 1102–1116. [Google Scholar] [CrossRef] [Scilit]
- Ju, F.; Ran, Y.; Zhu, L.; Cheng, X.; Gao, H.; Xi, X.; Yang, Z.; Zhang, S. Increased BBB Permeability Enhances Activation of Microglia and Exacerbates Loss of Dendritic Spines After Transient Global Cerebral Ischemia. Front. Cell. Neurosci. 2018, 12, 236. [Google Scholar] [CrossRef] [Scilit]
- Zhang, M.; Guo, B.; Zhang, X.; Han, D.; Lv, L.; Yan, X.; Su, C.; Chai, D.; Zhao, N.; Yan, X.; et al. IFP35, a Novel DAMP, Aggravates Neuroinflammation Following Acute Ischemic Stroke via TLR4/NF-κB/NLRP3 Signaling. J. Neuroinflamm. 2025, 22, 164. [Google Scholar] [CrossRef] [Scilit]
- Rodriguez-Baena, F.J.; Marquez-Galera, A.; Ballesteros-Martinez, P.; Castillo, A.; Diaz, E.; Moreno-Bueno, G.; Lopez-Atalaya, J.P.; Sanchez-Laorden, B. Microglial Reprogramming Enhances Antitumor Immunity and Immunotherapy Response in Melanoma Brain Metastases. Cancer Cell 2025, 43, 413–427.e9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, T.; Zhang, L.; Joo, D.; Sun, S.-C. NF-κB Signaling in Inflammation. Signal Transduct. Target. Ther. 2017, 2, 17023. [Google Scholar] [CrossRef] [Scilit]
- Seo, J.H.; Maki, T.; Maeda, M.; Miyamoto, N.; Liang, A.C.; Hayakawa, K.; Pham, L.-D.D.; Suwa, F.; Taguchi, A.; Matsuyama, T.; et al. Oligodendrocyte Precursor Cells Support Blood-Brain Barrier Integrity via TGF-β Signaling. PLoS ONE 2014, 9, e103174. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Niu, J.; Tsai, H.-H.; Hoi, K.K.; Huang, N.; Yu, G.; Kim, K.; Baranzini, S.E.; Xiao, L.; Chan, J.R.; Fancy, S.P.J. Aberrant Oligodendroglial-Vascular Interactions Disrupt the Blood-Brain Barrier, Triggering CNS Inflammation. Nat. Neurosci. 2019, 22, 709–718. [Google Scholar] [CrossRef] [Scilit]
- Zou, P.; Wu, C.; Liu, T.C.-Y.; Duan, R.; Yang, L. Oligodendrocyte Progenitor Cells in Alzheimer’s Disease: From Physiology to Pathology. Transl. Neurodegener. 2023, 12, 52. [Google Scholar] [CrossRef] [Scilit]
- Donovan, M.J.; Lin, M.I.; Wiegn, P.; Ringstedt, T.; Kraemer, R.; Hahn, R.; Wang, S.; Ibañez, C.F.; Rafii, S.; Hempstead, B.L. Brain Derived Neurotrophic Factor Is an Endothelial Cell Survival Factor Required for Intramyocardial Vessel Stabilization. Dev. Camb. Engl. 2000, 127, 4531–4540. [Google Scholar] [CrossRef] [Scilit]
- Lei, M.; Liu, Q.; Nie, J.; Huang, R.; Mei, Y.; Pan, D.; Chen, Y.; Liu, W. Impact and Mechanisms of Action of BDNF on Neurological Disorders, Cancer, and Cardiovascular Diseases. CNS Neurosci. Ther. 2024, 30, e70138. [Google Scholar] [CrossRef] [Scilit]
- Wang, X. Pleiotrophin: Activity and Mechanism. Adv. Clin. Chem. 2020, 98, 51–89. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Kundu, S.; Feenstra, T.; Li, X.; Jin, C.; Laaniste, L.; El Hassan, T.E.A.; Ohlin, K.E.; Yu, D.; Olofsson, T.; et al. Pleiotrophin Promotes Vascular Abnormalization in Gliomas and Correlates with Poor Survival in Patients with Astrocytomas. Sci. Signal. 2015, 8, ra125. [Google Scholar] [CrossRef] [Scilit]
- Shan, Y.; Tan, S.; Lin, Y.; Liao, S.; Zhang, B.; Chen, X.; Wang, J.; Deng, Z.; Zeng, Q.; Zhang, L.; et al. The Glucagon-like Peptide-1 Receptor Agonist Reduces Inflammation and Blood-Brain Barrier Breakdown in an Astrocyte-Dependent Manner in Experimental Stroke. J. Neuroinflamm. 2019, 16, 242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Subhramanyam, C.S.; Wang, C.; Hu, Q.; Dheen, S.T. Microglia-Mediated Neuroinflammation in Neurodegenerative Diseases. Semin. Cell Dev. Biol. 2019, 94, 112–120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, S.; Anshita, D.; Ravichandiran, V. MCP-1: Function, Regulation, and Involvement in Disease. Int. Immunopharmacol. 2021, 101, 107598. [Google Scholar] [CrossRef] [Scilit]
- Okekawa, A.; Wada, T.; Onogi, Y.; Takeda, Y.; Miyazawa, Y.; Sasahara, M.; Tsuneki, H.; Sasaoka, T. Platelet-Derived Growth Factor Signaling in Pericytes Promotes Hypothalamic Inflammation and Obesity. Mol. Med. 2024, 30, 21. [Google Scholar] [CrossRef] [Scilit]
- Zhou, C.; Gao, Y.; Ding, P.; Wu, T.; Ji, G. The Role of CXCL Family Members in Different Diseases. Cell Death Discov. 2023, 9, 212. [Google Scholar] [CrossRef] [Scilit]
- Prasad, M.; Xu, J.; Agranat, J.S.; Xia, W.; Daley, S.; Ness, S.; Chen, X.; Siegel, N.H.; Stein, T.D.; Chung, J.; et al. Upregulation of Neuroinflammatory Protein Biomarkers in Acute Rhegmatogenous Retinal Detachments. Life 2022, 13, 118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, C.; Liu, J.; Wu, B.; Shen, T.; Fan, J.; Lin, Y.; Li, K.; Guo, Y.; Shang, Y.; Zhou, B.; et al. Blockage of CCL3 with Neutralizing Antibody Reduces Neuroinflammation and Reverses Alzheimer Disease Phenotypes. Brain. Behav. Immun. 2025, 128, 400–415. [Google Scholar] [CrossRef] [Scilit]
- Zeng, Z.; Lan, T.; Wei, Y.; Wei, X. CCL5/CCR5 Axis in Human Diseases and Related Treatments. Genes Dis. 2022, 9, 12–27. [Google Scholar] [CrossRef] [Scilit]
- Matthews, A.N.; Friend, D.S.; Zimmermann, N.; Sarafi, M.N.; Luster, A.D.; Pearlman, E.; Wert, S.E.; Rothenberg, M.E. Eotaxin Is Required for the Baseline Level of Tissue Eosinophils. Proc. Natl. Acad. Sci. USA 1998, 95, 6273–6278. [Google Scholar] [CrossRef] [Scilit]
- Fülle, L.; Offermann, N.; Hansen, J.N.; Breithausen, B.; Erazo, A.B.; Schanz, O.; Radau, L.; Gondorf, F.; Knöpper, K.; Alferink, J.; et al. CCL17 Exerts a Neuroimmune Modulatory Function and Is Expressed in Hippocampal Neurons. Glia 2018, 66, 2246–2261. [Google Scholar] [CrossRef] [Scilit]
- Marques, R.E.; Guabiraba, R.; Russo, R.C.; Teixeira, M.M. Targeting CCL5 in Inflammation. Expert Opin. Ther. Targets 2013, 17, 1439–1460. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aldinucci, D.; Colombatti, A. The Inflammatory Chemokine CCL5 and Cancer Progression. Mediat. Inflamm. 2014, 2014, 292376. [Google Scholar] [CrossRef] [Scilit]
- Taylor, K.R.; Monje, M. Neuron-Oligodendroglial Interactions in Health and Malignant Disease. Nat. Rev. Neurosci. 2023, 24, 733–746. [Google Scholar] [CrossRef] [Scilit]
- Moon, S.; Sarmento, C.V.M.; Smirnova, I.V.; Colgrove, Y.; Lai, S.-M.; Lyons, K.E.; Liu, W. A Pilot Randomized Clinical Trial Examining the Effects of Qigong on Inflammatory Status and Sleep Quality in People with Parkinson’s Disease. J. Bodyw. Mov. Ther. 2024, 40, 1002–1007. [Google Scholar] [CrossRef] [Scilit]
- Saadh, M.J.; Muhammad, F.A.; Singh, A.; Mustafa, M.A.; Al Zuhairi, R.A.H.; Ghildiyal, P.; Hashim, G.; Alsaikhan, F.; Khalilollah, S.; Akhavan-Sigari, R. MicroRNAs Modulating Neuroinflammation in Parkinson’s Disease. Inflammation 2025, 48, 1042–1062. [Google Scholar] [CrossRef] [Scilit]
- Domènech, M.; Hernández, A.; Plaja, A.; Martínez-Balibrea, E.; Balañà, C. Hypoxia: The Cornerstone of Glioblastoma. Int. J. Mol. Sci. 2021, 22, 12608. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Huang, H.; Cui, Y.; Li, W.; Zhang, S.; Chen, Y. Study on the Mechanism of Capillary Leakage Caused by Hypoxia-Inducible Factor-1α through Inducing High Expression of Matrix Metalloproteinase-9. J. Oncol. 2021, 2021, 9130650. [Google Scholar] [CrossRef] [Scilit]
- Zhao, Y.; Tang, X.; Lei, T.; Fu, D.; Zhang, H. Lipocalin-2 Promotes Breast Cancer Brain Metastasis by Enhancing Tumor Invasion and Modulating Brain Microenvironment. Front. Oncol. 2024, 14, 1448089. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moser, K.V.; Reindl, M.; Blasig, I.; Humpel, C. Brain Capillary Endothelial Cells Proliferate in Response to NGF, Express NGF Receptors and Secrete NGF after Inflammation. Brain Res. 2004, 1017, 53–60. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heymans, M.; Figueiredo, R.; Dehouck, L.; Francisco, D.; Sano, Y.; Shimizu, F.; Kanda, T.; Bruggmann, R.; Engelhardt, B.; Winter, P.; et al. Contribution of Brain Pericytes in Blood-Brain Barrier Formation and Maintenance: A Transcriptomic Study of Cocultured Human Endothelial Cells Derived from Hematopoietic Stem Cells. Fluids Barriers CNS 2020, 17, 48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gutowicz, M. Wpływ reaktywnych form tlenu na ośrodkowy uklad nerwowy. Postępy Hig. Med. Dośw. 2011, 65, 104–113. [Google Scholar] [CrossRef] [Scilit]
- Nelson, R.A.; Rhee, E.K.; Alaeddine, M.; Nikkhah, M. Advances in Biomaterials for Promoting Vascularization. Curr. Stem Cell Rep. 2022, 8, 184–196. [Google Scholar] [CrossRef] [Scilit]
- Xia, D.-Y.; Yuan, J.-L.; Jiang, X.-C.; Qi, M.; Lai, N.-S.; Wu, L.-Y.; Zhang, X.-S. SIRT1 Promotes M2 Microglia Polarization via Reducing ROS-Mediated NLRP3 Inflammasome Signaling After Subarachnoid Hemorrhage. Front. Immunol. 2021, 12, 770744. [Google Scholar] [CrossRef] [Scilit]
- Rashid, M.; Zadeh, L.R.; Baradaran, B.; Molavi, O.; Ghesmati, Z.; Sabzichi, M.; Ramezani, F. Up-down Regulation of HIF-1α in Cancer Progression. Gene 2021, 798, 145796. [Google Scholar] [CrossRef] [Scilit]
- Vahsen, B.F.; Nalluru, S.; Morgan, G.R.; Farrimond, L.; Carroll, E.; Xu, Y.; Cramb, K.M.L.; Amein, B.; Scaber, J.; Katsikoudi, A.; et al. C9orf72-ALS Human iPSC Microglia Are pro-Inflammatory and Toxic to Co-Cultured Motor Neurons via MMP9. Nat. Commun. 2023, 14, 5898. [Google Scholar] [CrossRef] [Scilit]
- Xu, J.; Zhao, W. Bidirectional Role of Pericytes in Ischemic Stroke. Brain Sci. 2025, 15, 605. [Google Scholar] [CrossRef] [Scilit]
- Tsao, C.-C.; Baumann, J.; Huang, S.-F.; Kindler, D.; Schroeter, A.; Kachappilly, N.; Gassmann, M.; Rudin, M.; Ogunshola, O.O. Pericyte Hypoxia-Inducible Factor-1 (HIF-1) Drives Blood-Brain Barrier Disruption and Impacts Acute Ischemic Stroke Outcome. Angiogenesis 2021, 24, 823–842. [Google Scholar] [CrossRef] [Scilit]
- Wu, J.; Yan, F.; Li, Y.; Liang, M.; Guo, Y.; Yang, M. Hypoxia Inducible Factor-1alpha Expression Correlates with Inflammatory Injury of Blood-Brain Barrier Which Influences Perihaematomal Edema after Intracerebral Hemorrhage. J. Stroke Cerebrovasc. Dis. 2025, 34, 108269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qannita, R.A.; Alalami, A.I.; Harb, A.A.; Aleidi, S.M.; Taneera, J.; Abu-Gharbieh, E.; El-Huneidi, W.; Saleh, M.A.; Alzoubi, K.H.; Semreen, M.H.; et al. Targeting Hypoxia-Inducible Factor-1 (HIF-1) in Cancer: Emerging Therapeutic Strategies and Pathway Regulation. Pharmaceuticals 2024, 17, 195. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Q.; Ma, Y.; Liu, J.; Zhang, D.; Ren, J.; Zhao, R.; Chang, J.; Guo, Z.-N.; Yang, Y. Biological Functions and Regulatory Mechanisms of Hypoxia-Inducible Factor-1α in Ischemic Stroke. Front. Immunol. 2021, 12, 801985. [Google Scholar] [CrossRef] [Scilit]
- Jamieson, J.J.; Lin, Y.; Malloy, N.; Soto, D.; Searson, P.C.; Gerecht, S. Hypoxia-Induced Blood-Brain Barrier Dysfunction Is Prevented by Pericyte-Conditioned Media via Attenuated Actomyosin Contractility and Claudin-5 Stabilization. FASEB J. Off. Publ. Fed. Am. Soc. Exp. Biol. 2022, 36, e22331. [Google Scholar] [CrossRef] [Scilit]
- Osaid, Z.; Haider, M.; Hamoudi, R.; Harati, R. Exosomes Interactions with the Blood–Brain Barrier: Implications for Cerebral Disorders and Therapeutics. Int. J. Mol. Sci. 2023, 24, 15635. [Google Scholar] [CrossRef] [Scilit]
- Izadi, N.; Solár, P.; Hašanová, K.; Zamani, A.; Akbar, M.S.; Mrázová, K.; Bartošík, M.; Kazda, T.; Hrstka, R.; Joukal, M. Breaking Boundaries: Role of the Brain Barriers in Metastatic Process. Fluids Barriers CNS 2025, 22, 3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, S.; Wang, H.; Yin, Y. Microglia Polarization from M1 to M2 in Neurodegenerative Diseases. Front. Aging Neurosci. 2022, 14, 815347. [Google Scholar] [CrossRef] [Scilit]
- Yang, M.; Li, J.; Gu, P.; Fan, X. The Application of Nanoparticles in Cancer Immunotherapy: Targeting Tumor Microenvironment. Bioact. Mater. 2020, 6, 1973–1987. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- You, L.; Wu, W.; Wang, X.; Fang, L.; Adam, V.; Nepovimova, E.; Wu, Q.; Kuca, K. The Role of Hypoxia-Inducible Factor 1 in Tumor Immune Evasion. Med. Res. Rev. 2021, 41, 1622–1643. [Google Scholar] [CrossRef] [Scilit]
- Cagney, D.N.; Martin, A.M.; Catalano, P.J.; Redig, A.J.; Lin, N.U.; Lee, E.Q.; Wen, P.Y.; Dunn, I.F.; Bi, W.L.; Weiss, S.E.; et al. Incidence and Prognosis of Patients with Brain Metastases at Diagnosis of Systemic Malignancy: A Population-Based Study. Neuro-oncology 2017, 19, 1511–1521. [Google Scholar] [CrossRef] [Scilit]
- Fidler, I.J. The Pathogenesis of Cancer Metastasis: The “seed and Soil” Hypothesis Revisited. Nat. Rev. Cancer 2003, 3, 453–458. [Google Scholar] [CrossRef] [Scilit]
- Coupland, L.A.; Parish, C.R. Platelets, Selectins, and the Control of Tumor Metastasis. Semin. Oncol. 2014, 41, 422–434. [Google Scholar] [CrossRef] [Scilit]
- Soekeland, G.; Schumacher, U. The Functional Role of Integrins during Intra- and Extravasation within the Metastatic Cascade. Mol. Cancer 2019, 18, 12. [Google Scholar] [CrossRef] [Scilit]
- Jassam, S.A.; Maherally, Z.; Smith, J.R.; Ashkan, K.; Roncaroli, F.; Fillmore, H.L.; Pilkington, G.J. TNF-α Enhancement of CD62E Mediates Adhesion of Non–Small Cell Lung Cancer Cells to Brain Endothelium via CD15 in Lung-Brain Metastasis. Neuro-oncology 2016, 18, 679–690. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rai, S.; Nejadhamzeeigilani, Z.; Gutowski, N.J.; Whatmore, J.L. Loss of the Endothelial Glycocalyx Is Associated with Increased E-Selectin Mediated Adhesion of Lung Tumour Cells to the Brain Microvascular Endothelium. J. Exp. Clin. Cancer Res. 2015, 34, 105. [Google Scholar] [CrossRef] [Scilit]
- Alsbrook, D.L.; Di Napoli, M.; Bhatia, K.; Biller, J.; Andalib, S.; Hinduja, A.; Rodrigues, R.; Rodriguez, M.; Sabbagh, S.Y.; Selim, M.; et al. Neuroinflammation in Acute Ischemic and Hemorrhagic Stroke. Curr. Neurol. Neurosci. Rep. 2023, 23, 407–431. [Google Scholar] [CrossRef] [Scilit]
- Chhichholiya, Y.; Ruthuparna, M.; Velagaleti, H.; Munshi, A. Brain Metastasis in Breast Cancer: Focus on Genes and Signaling Pathways Involved, Blood–Brain Barrier and Treatment Strategies. Clin. Transl. Oncol. 2023, 25, 1218–1241. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilhelm, I.; Fazakas, C.; Molnár, K.; Végh, A.G.; Haskó, J.; Krizbai, I.A. Foe or Friend? Janus-Faces of the Neurovascular Unit in the Formation of Brain Metastases. J. Cereb. Blood Flow Metab. Off. J. Int. Soc. Cereb. Blood Flow Metab. 2018, 38, 563–587. [Google Scholar] [CrossRef] [Scilit]
- Hosonaga, M.; Saya, H.; Arima, Y. Molecular and Cellular Mechanisms Underlying Brain Metastasis of Breast Cancer. Cancer Metastasis Rev. 2020, 39, 711–720. [Google Scholar] [CrossRef] [Scilit]
- Guo, H.; Fan, Z.; Wang, S.; Ma, L.; Wang, J.; Yu, D.; Zhang, Z.; Wu, L.; Peng, Z.; Liu, W.; et al. Astrocytic A1/A2 Paradigm Participates in Glycogen Mobilization Mediated Neuroprotection on Reperfusion Injury after Ischemic Stroke. J. Neuroinflamm. 2021, 18, 230. [Google Scholar] [CrossRef] [Scilit]
- Zhou, T.; Yan, Y.; Lin, M.; Zeng, C.; Mao, X.; Zhu, Y.; Han, J.; Li, D.-D.; Zhang, J. Astrocyte Involvement in Brain Metastasis: From Biological Mechanisms to Therapeutic Strategies. Cancer Metastasis Rev. 2025, 44, 60. [Google Scholar] [CrossRef] [Scilit]
- Fredriksson, L.; Lawrence, D.A.; Medcalf, R.L. tPA Modulation of the Blood-Brain Barrier: A Unifying Explanation for the Pleiotropic Effects of tPA in the CNS? Semin. Thromb. Hemost. 2017, 43, 154–168. [Google Scholar] [CrossRef] [Scilit]
- Liu, L.; He, Y.; Du, H.; Tang, M.; Wang, T.; Tan, J.; Zha, L.; Yang, L.; Ashrafizadeh, M.; Tian, Y.; et al. Biological Profile of Breast Cancer Brain Metastasis. Acta Neuropathol. Commun. 2025, 13, 78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ye, L.; Sun, L.; Zhong, X.; Chen, X.; Hu, S.; Xu, R.; Zeng, X.; Xie, W.; Kong, H. The Structure of Blood–Tumor Barrier and Distribution of Chemotherapeutic Drugs in Non-Small Cell Lung Cancer Brain Metastases. Cancer Cell Int. 2021, 21, 556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sandler, C.X.; Matsuyama, M.; Jones, T.L.; Bashford, J.; Langbecker, D.; Hayes, S.C. Physical Activity and Exercise in Adults Diagnosed with Primary Brain Cancer: A Systematic Review. J. Neurooncol. 2021, 153, 1–14. [Google Scholar] [CrossRef] [Scilit]
- Shu, C.; Han, H.; Li, H.; Wei, L.; Wu, H.; Li, C.; Xie, X.; Zhang, B.; Li, Z.; Chen, X.; et al. Cancer Risk Subsequent to Cardiovascular Disease: A Prospective Population-Based Study and Meta-Analysis. BMC Med. 2025, 23, 192. [Google Scholar] [CrossRef] [Scilit]
- Chen, L.; Li, L.; Zhou, C.; Chen, X.; Cao, Y. Adenosine A2A Receptor Activation Reduces Brain Metastasis via SDF-1/CXCR4 Axis and Protecting Blood-Brain Barrier. Mol. Carcinog. 2020, 59, 390–398. [Google Scholar] [CrossRef] [Scilit]
- Zhu, L.; Yang, F.; Wang, G.; Li, Q. CXC Motif Chemokine Receptor Type 4 Disrupts Blood-Brain Barrier and Promotes Brain Metastasis Through Activation of the PI3K/AKT Pathway in Lung Cancer. World Neurosurg. 2022, 166, e369–e381. [Google Scholar] [CrossRef] [Scilit]
- Gwak, D.-S.; Hwang, Y.-H.; Kim, Y.-W. Case Report: Brain Metastasis Confined to the Infarcted Area Following Stroke. Front. Neurol. 2021, 11, 617142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amisano, P.; Ciacciarelli, A.; Lorenzano, S.; Berto, I.; Belcastro, S.; Toni, D.; De Michele, M. Ischemic Stroke of Undetermined Source as a Priming Event for Brain Metastasis: A Case Report and Systematic Literature Review. Front. Oncol. 2025, 15, 1638420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Atallah, O.; Chaurasia, B. Brain Metastasis Localized to the Same Area of Infarction: Illustrative Case. J. Neurosurg. Case Lessons 2023, 6, CASE23325. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.; Jung, G.; Kim, H.G.; Kim, J.Y.; Yang, G.Y.; Kim, Y.Z. Role of Cancer Emboli as a Metastatic Core on the Growth of Brain Metastasis in Patients with Non-Small Cell Lung Cancer. J. Neurointensive Care 2020, 3, 12–19. [Google Scholar] [CrossRef] [Scilit]
- Yaghmour, W.; Kurdi, M.E.; Baeesa, S.S. De Novo Glioblastoma in the Territory of a Recent Middle Cerebral Artery Infarction and a Residual Meningioma: Pathogenesis Revisited. World J. Surg. Oncol. 2016, 14, 112. [Google Scholar] [CrossRef] [Scilit]
- López-González, A.; Galeano, I.; Gutiérrez, A.; Giner, R.; Alvarez-Garijo, J.A.; Cabanes, J. Association between cerebral infarction and malignant glioma. Rev. Neurol. 2005, 40, 34–37. [Google Scholar]
- Wojtasiewicz, T.J.; Ducruet, A.F.; Noticewala, S.S.; Canoll, P.; McKhann, G.M. De Novo Glioblastoma in the Territory of a Prior Middle Cerebral Artery Infarct. Case Rep. Neurol. Med. 2013, 2013, 356526. [Google Scholar] [CrossRef] [Scilit]
- Ojemakinde, O.; Gonzalez Toledo, E.; Wilson, J. A Case of Glioblastoma in Infarcted Brain. J. La. State Med. Soc. Off. Organ La. State Med. Soc. 2013, 165, 30–32. [Google Scholar]
- Butler, H.; Gray, E.; Cameron, J.M.; Brennan, P.; Hall, P.S.; Lishman, A.; Karunaratne, P.; Tramonti, G.; Vallet, M.; Baker, M. Earlier Brain Tumor Detection: Assessing the Impact on Survival, Recurrence, Inpatient Length of Stay and Neurological Deficit. J. Clin. Oncol. 2025, 43, e23268. [Google Scholar] [CrossRef] [Scilit]
- Tan, X.; Zhang, K.; Shi, W.; Tang, Z. Research Progress on the Regulation and Mechanism of Borneol on the Blood-Brain Barrier in Pathological States: A Narrative Review Focused on Ischemic Stroke and Cerebral Glioma. Transl. Cancer Res. 2023, 12, 3198–3209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, S.; Shi, J.; Wang, X.; Huang, C.; Huang, Y.; Xu, J.; Jiang, Y.; Cao, L.; Xie, T.; Wang, Y.; et al. Atractylon Inhibits the Tumorigenesis of Glioblastoma through SIRT3 Signaling. Am. J. Cancer Res. 2022, 12, 2310–2322. [Google Scholar] [PubMed]
- Yang, X.; Zhang, Y.; Geng, K.; Yang, K.; Shao, J.; Xia, W. Sirt3 Protects Against Ischemic Stroke Injury by Regulating HIF-1α/VEGF Signaling and Blood-Brain Barrier Integrity. Cell. Mol. Neurobiol. 2021, 41, 1203–1215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lv, P.; Hu, Y.; Ding, L.; Xiang, W. Puerarin Triggers Sensitivity to Ferroptosis in Glioblastoma Cells by Activating SIRT3/NCOA4-Dependent Autophagy. Int. Immunopharmacol. 2025, 149, 114246. [Google Scholar] [CrossRef] [Scilit]
- Shuai, S.; Liu, S.; Liu, X.; Zhang, G.; Zheng, Q.; Yue, P.; Yang, M.; Hu, P. Essential Oil of Ligusticum Chuanxiong Hort. Regulated P-Gp Protein and Tight Junction Protein to Change Pharmacokinetic Parameters of Temozolomide in Blood, Brain and Tumor. J. Ethnopharmacol. 2022, 298, 115646. [Google Scholar] [CrossRef] [Scilit]
- Ke, G.; Hu, P.; Xiong, H.; Zhang, J.; Xu, H.; Xiao, C.; Liu, Y.; Cao, M.; Zheng, Q. Enhancing Temozolomide Efficacy in GBM: The Synergistic Role of Chuanxiong Rhizoma Essential Oil. Phytomedicine 2025, 140, 156575. [Google Scholar] [CrossRef] [Scilit]
- Harris, W.J.; Asselin, M.-C.; Hinz, R.; Parkes, L.M.; Allan, S.; Schiessl, I.; Boutin, H.; Dickie, B.R. In Vivo Methods for Imaging Blood–Brain Barrier Function and Dysfunction. Eur. J. Nucl. Med. Mol. Imaging 2023, 50, 1051–1083. [Google Scholar] [CrossRef] [Scilit]
- Chung, K.J.; Abdelhafez, Y.G.; Spencer, B.A.; Jones, T.; Tran, Q.; Nardo, L.; Chen, M.S.; Sarkar, S.; Medici, V.; Lyo, V.; et al. Quantitative PET Imaging and Modeling of Molecular Blood-Brain Barrier Permeability. Nat. Commun. 2025, 16, 3076. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Simone, M.; Choucha, A.; Ranalli, C.; Pecoraro, G.; Appay, R.; Chinot, O.L.; Dufour, H.; Iaconetta, G. Astrocytomas IDH-Mutant of Posterior Cranial Fossa, Clinical Presentation, Imaging Features and Onco-Functional Balance in Surgical Management. Neurosurg. Rev. 2025, 48, 271. [Google Scholar] [CrossRef] [Scilit]
- Wilcox, N.S.; Amit, U.; Reibel, J.B.; Berlin, E.; Howell, K.; Ky, B. Cardiovascular Disease and Cancer: Shared Risk Factors and Mechanisms. Nat. Rev. Cardiol. 2024, 21, 617–631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, J.; Liu, Z.; Huang, T.; Wang, Y.; Song, M.M.; Song, T.; Long, G.; Zhang, X.; Li, X.; Zhang, L. Cerebrospinal Fluid Circulating Tumor DNA Depicts Profiling of Brain Metastasis in NSCLC. Mol. Oncol. 2022, 17, 810–824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nägele, F.L.; Scheldeman, L.; Wouters, A.; Heinze, M.; Petersen, M.; Schlemm, E.; Schell, M.; Ebinger, M.; Endres, M.; Fiebach, J.B.; et al. Blood-Brain Barrier Leakage in the Penumbra Is Associated with Infarction on Follow-Up Imaging in Acute Ischemic Stroke. Stroke 2025, 56, 1832–1842. [Google Scholar] [CrossRef] [Scilit] [PubMed]
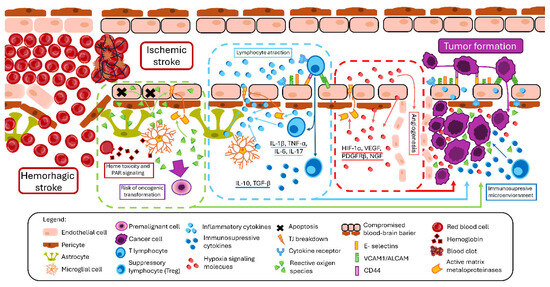
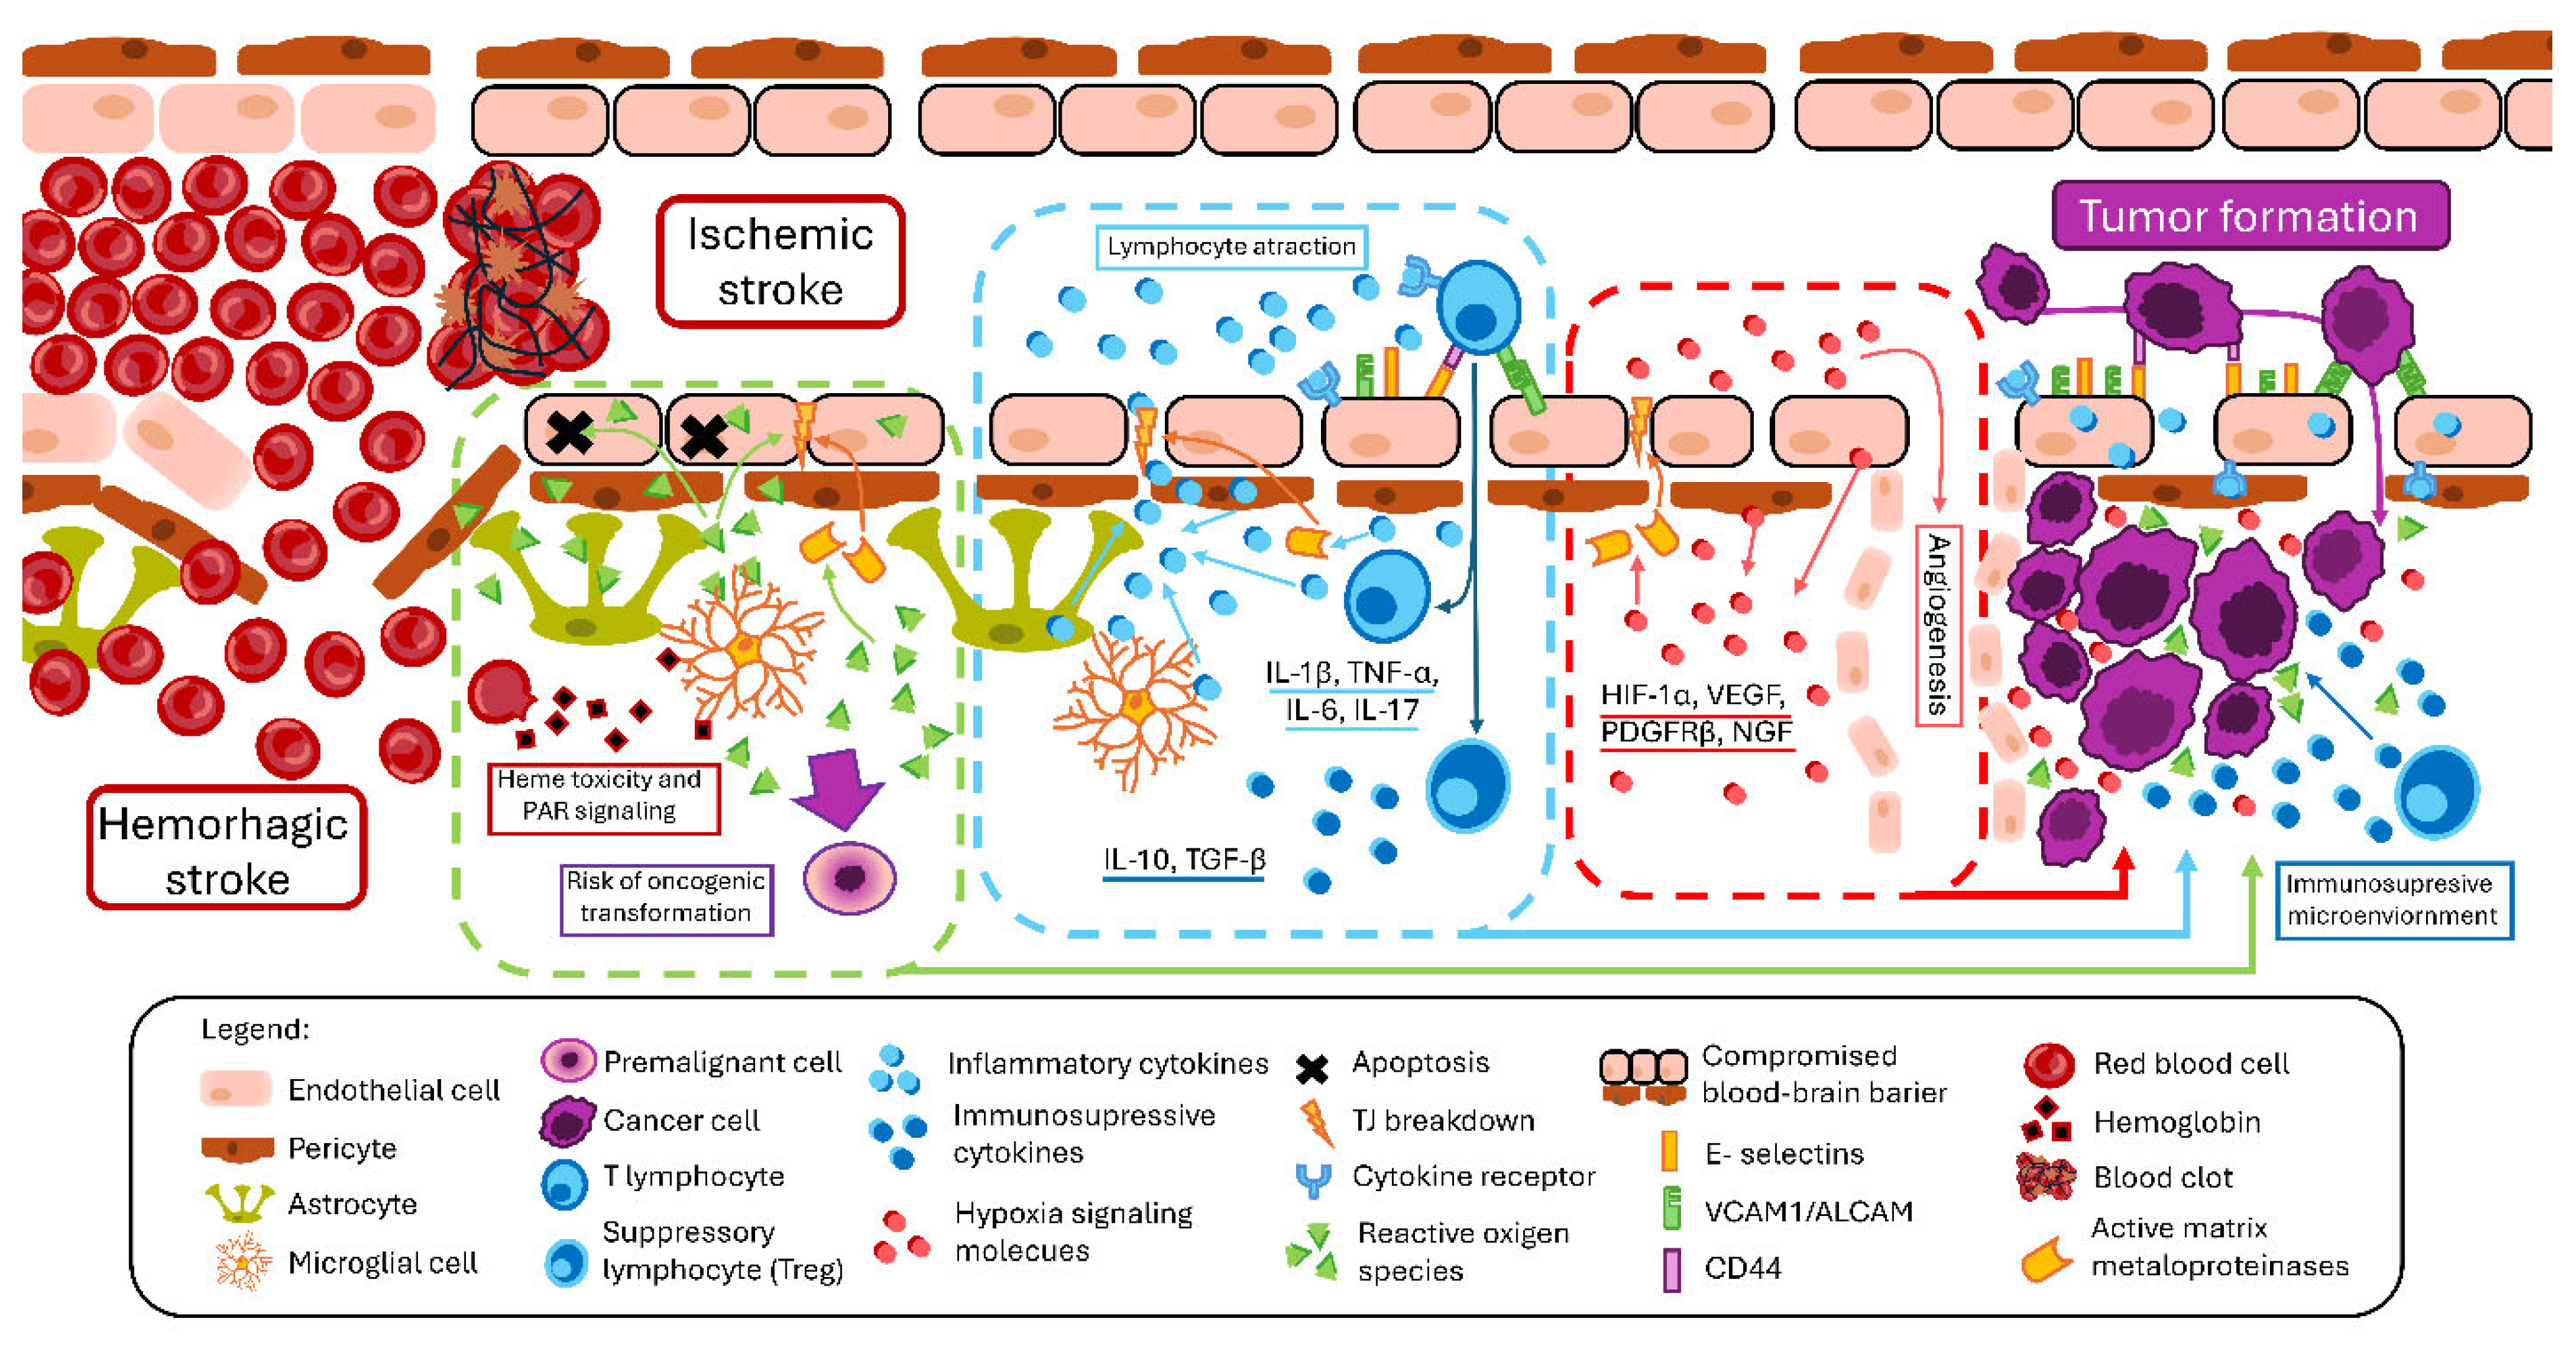
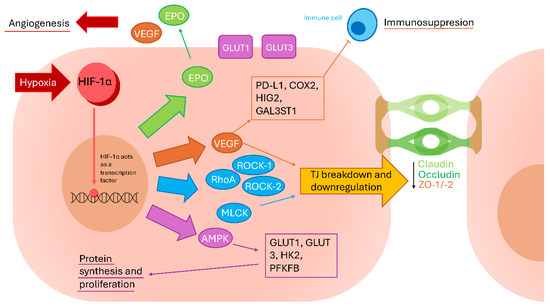
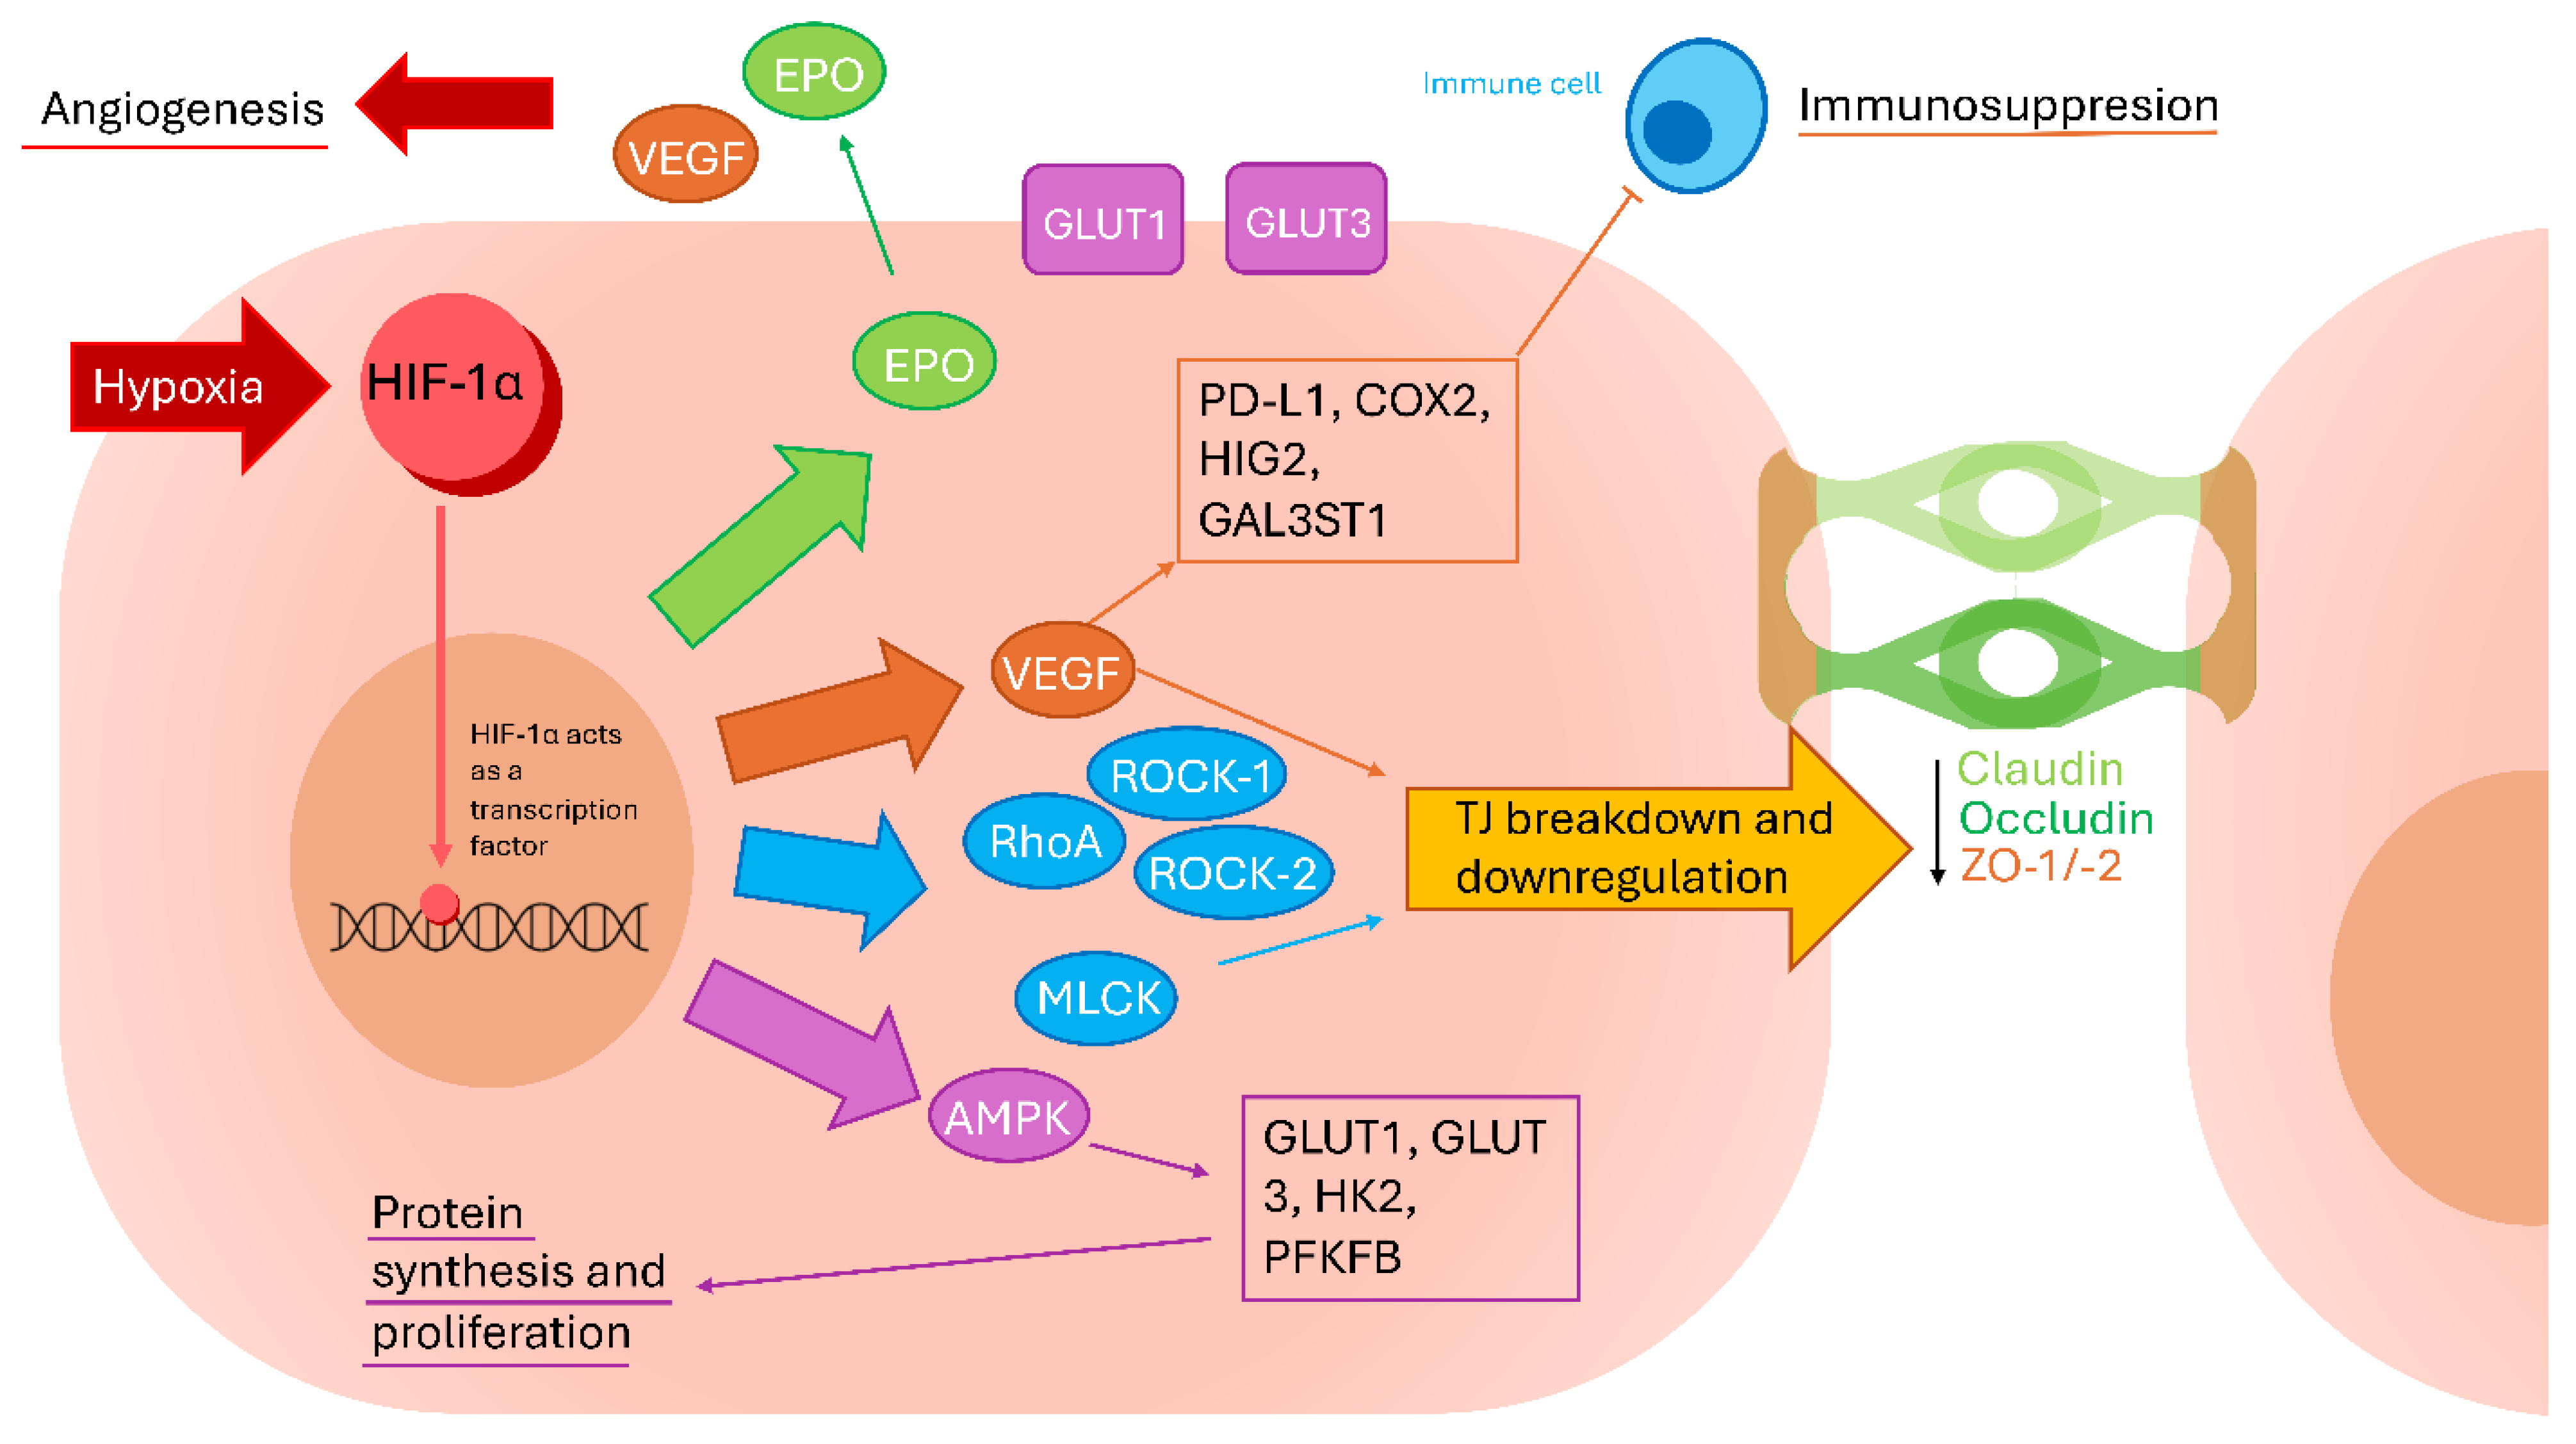
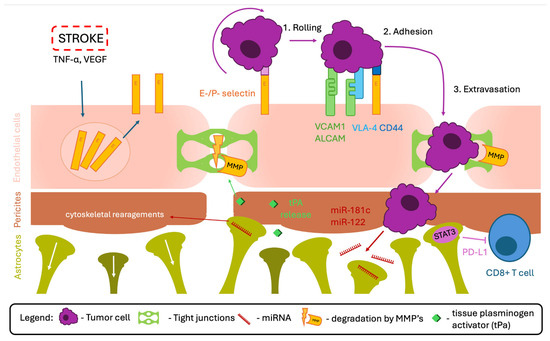
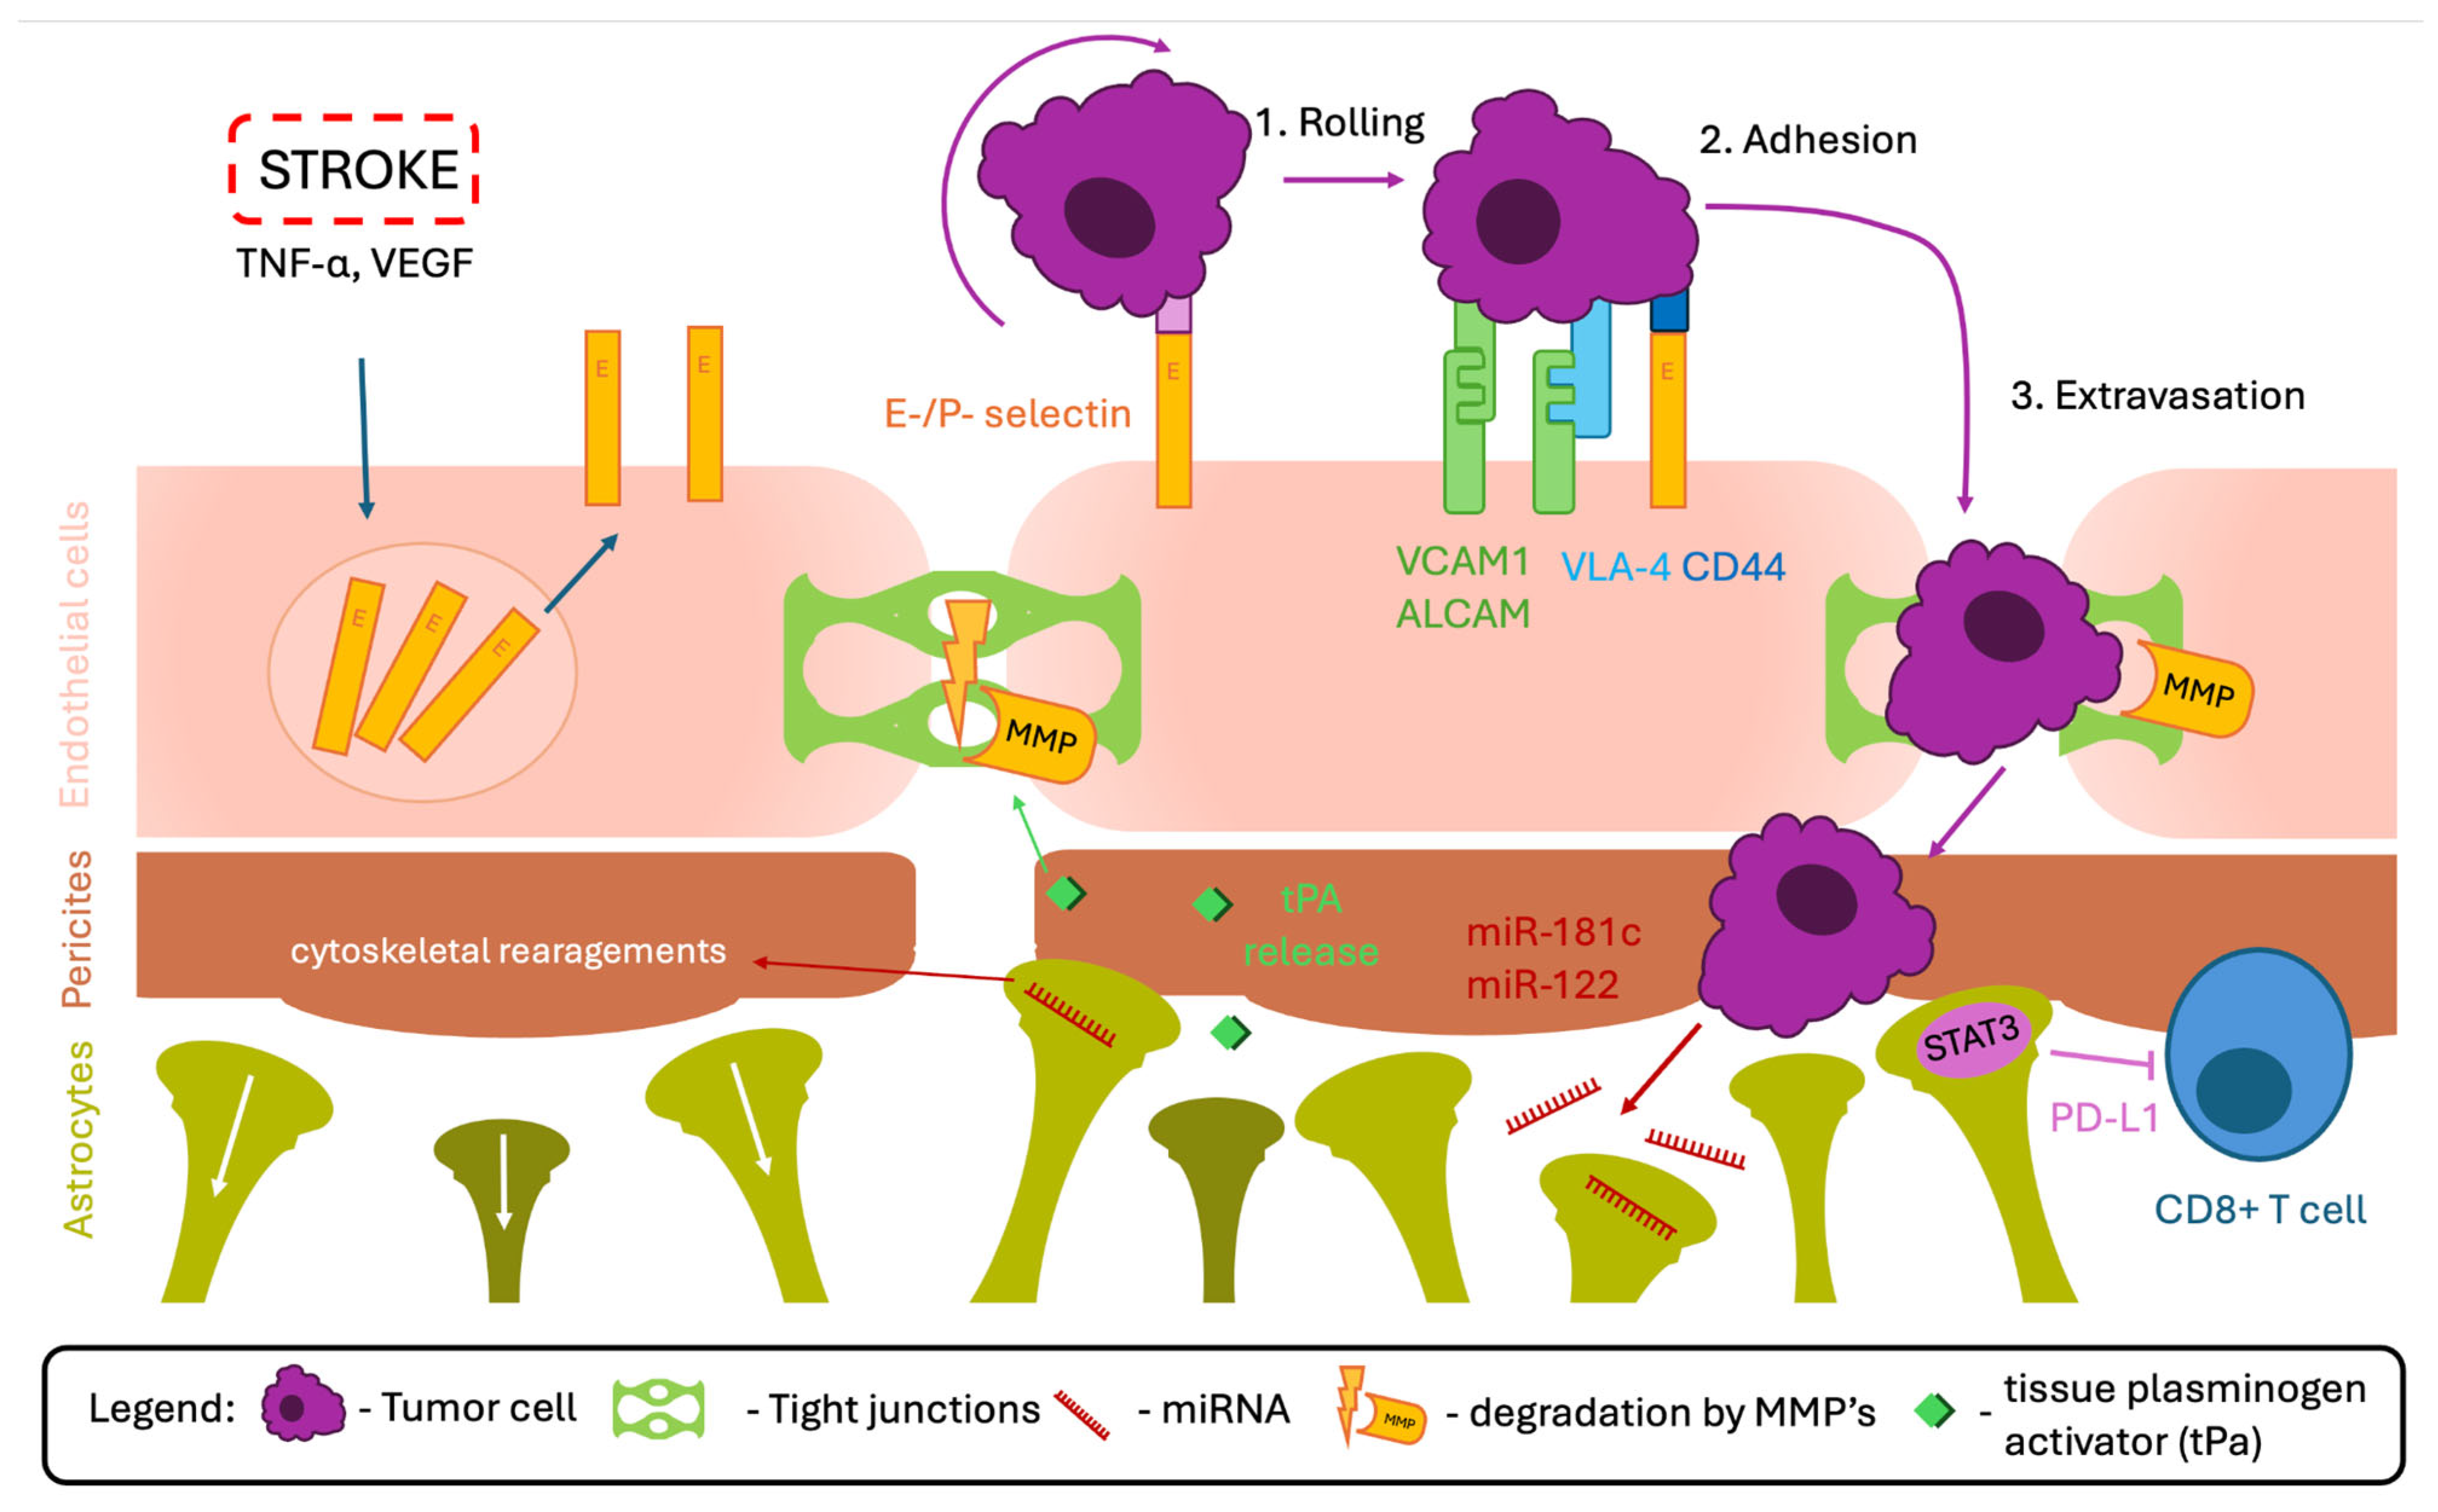

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.