


Abstract
Giant cell tumor of bone (GCTB) is a distinctive, intermediate-grade primary bone neoplasm defined by a neoplastic mesenchymal stromal compartment and a prominent osteoclast-rich microenvironment. Although histologically benign, GCTB is clinically consequential due to its locally destructive behavior, propensity for recurrence, and rare capacity for metastasis and malignant transformation. Over the past decade, the identification of recurrent H3F3A p.G34 mutations has fundamentally reshaped the understanding of GCTB pathogenesis, establishing the stromal cell as the true neoplastic driver and positioning the tumor as a paradigmatic epigenetically driven osteolytic disease. This narrative review focus on biology, pathophysiology, and histopathology in the era of H3F3A. H3F3A-mutant stromal cells orchestrate pathological osteoclastogenesis through dysregulated RANKL signaling and chromatin reprogramming, giving rise to the characteristic cellular admixture of osteoclast-type giant cells, mononuclear histiocytic cells, and neoplastic stromal elements. The targeted inhibition of osteoclast activity with denosumab has transformed clinical management, inducing profound morphological changes and bone formation. However, its long-term impact on local control, recurrence patterns, and malignant progression remains unclear. Collectively, GCTB exemplifies a molecularly defined bone tumor in which advances in epigenetic biology and tumor–microenvironment interactions have directly influenced diagnostic practice and therapeutic strategy. Ongoing challenges include refining risk stratification, optimizing treatment sequencing, and clarifying the biological consequences of sustained osteoclast suppression.
1. Introduction
Giant cell tumor of bone (GCTB) is a primary bone neoplasm defined by the presence of mononuclear neoplastic stromal cells and numerous reactive osteoclast-type giant cells. Its incidence is approximately 1.8 cases per million per year in Western populations, being higher in Asia, possibly reflecting genetic or environmental factors or differences in diagnostic classification [1,2,3,4]. In fact, while demographic factors such as population age structure and access to specialized diagnostics partially explain these differences, emerging evidence suggests that integrating molecular pathology with epidemiological data may uncover population-specific biological or genetic susceptibilities that influence tumor development and clinical behavior [5,6]. GCTB accounts for approximately 4 to 10% of all primary bone tumors [7,8,9] and affects predominantly adults aged between 20 and 45 years [1,10]. The tumor is slightly predominant in females [1,10,11,12]. Typical symptoms can include the insidious onset of localized pain, swelling and tenderness, decreased range of motion, mechanical symptoms when the tumor is near joints, and pathological fractures [10,13].
The biological nature of GCTB remained debated for decades due to the mixture of reactive multinucleated giant cells and mononuclear cells [14,15,16]. Although histologically benign, the tumor is locally aggressive and capable of pulmonary metastasis [17,18,19,20], placing it in the category of “intermediate locally aggressive” according to the World Health Organization (WHO) [21,22]. The tumor’s clinical course is unpredictable, and despite lacking intrinsic metastatic biology, a small percentage of cases disseminate to the lung. Local aggressiveness and recurrence rates remain significant, particularly after intralesional procedures [7,18,20]. In fact, recurrence rates after surgical curettage may reach 30 to 50% depending on the adequacy of mechanical removal, use of adjuvants, anatomical localization, and epigenetic signatures from H3.3 histone A (H3F3A)-mutated stromal cells [23,24,25]. Malignant transformation is rare [26,27], and histologically, transformed lesions show high-grade sarcomatous features, often losing the classic giant cell pattern [26]. Pulmonary metastases occur in 1 to 4% of cases with the metastatic mechanism remaining unclear, but it may involve stromal cell clusters entering venous circulation [28].
The identification of recurrent H3F3A mutations in neoplastic stromal cells has revolutionized the conceptualization of GCTB [29,30,31,32], providing a unifying pathogenic mechanism and establishing immunohistochemistry for mutation H3.3 G34W as a decisive diagnostic tool [29,30,31,32]. In fact, the identification of driver mutations in H3F3A conclusively positioned the mononuclear stromal cell as the true neoplastic component [33].
From a clinical standpoint, GCTB typically arises in the epiphysis of long bones, especially the distal femur, proximal tibia, and distal radius (these three locations contribute to approximately 60% of cases), though axial skeleton involvement presents unique management challenges [34,35,36]. Lesions near joints often present late because of slow cortical breakthrough and joint-sparing expansion into cancellous bone [7,13,37]. GCTB is uncommon in the craniofacial region, and its clinical presentation can complicate diagnosis. Because the jaw bones can harbor a wide range of cysts and tumors of different origins, lesions lacking odontogenic features require careful investigation. Tumor biomarkers may assist surgeons in developing an appropriate treatment plan and predicting disease prognosis [38,39,40].
A hallmark of the disease is aggressive osteolysis driven by the overexpression of receptor activator of nuclear factor kappa B ligand (RANKL) in stromal cells, resulting in significant bone destruction and functional impairment [41,42,43,44]. Interestingly, GCTB represents a paradigm of paracrine neoplasia wherein neoplastic stromal cells orchestrate the recruitment and fusion of osteoclast precursors via excessive RANKL expression, leading to profound osteolysis [41,44,45,46,47]. Accordingly, the tumor’s characteristic giant cells function as reactive effectors rather than neoplastic elements and are predominantly of macrophage origin (CD68-positive, CD163-negative), and their phenotype aligns more with osteoclast-like cells in bone lesions than with macrophage polykaryons in extraosseous lesions [48].
From a pathological perspective, GCTB represents a model of tumor–microenvironment interaction, where neoplastic cells utilize osteoclastogenic signaling to remodel bone for their own expansion [44,49,50,51]. Understanding this biology is essential to modern clinical management, particularly in the era of denosumab, which directly targets RANKL and reshapes tumor morphology [42,52,53].
Proposed risk factors for the development of this neoplasm include previous trauma, Paget’s disease of bone, genetic predisposition, and radiation exposure. Although these associations are not fully understood, they suggest that both environmental and genetic factors may contribute to tumor pathogenesis [26,54]. In this context, the aim of this narrative review is to synthesize current evidence on the biology, pathophysiology, and histopathology of GCTB.
2. Search of Existing Evidence
A structured narrative review methodology was adopted to ensure rigor and reproducibility. The literature was identified through a search in PubMed/MEDLINE, Scopus and Web of Science. We also used the WHO Classification of Soft Tissue and Bone Tumors (5th edition, 2020) [22]. Search terms included: “giant cell tumor of bone”, “H3F3A”, “osteoclastogenesis”, “RANKL”, “giant cell neoplasm”, “denosumab”, “histopathology”, “epigenetic regulation”, and “bone tumor”.
Inclusion criteria included: English-language, peer-reviewed studies; pertinence to biology, pathophysiology, histopathology, diagnosis, imaging, or treatment; and publication date of 1990–2025, with a preference for the post-2010 molecular literature. On the other hand, exclusion criteria included: case reports without mechanistic insights; non-skeletal giant cell lesions; pediatric epiphyseal cystic lesions; and articles focusing on giant cell-rich sarcomas (except for differential diagnosis).
The content was analyzed and involved the following thematic areas: molecular biology and genetics; tumor microenvironment; osteoclastogenesis; histopathology; radiology and clinical behavior; and therapeutic implications.
The key references are described in Appendix A (Table A1).
3. Bone Homeostasis in Normal Physiology
Bone is a rigid and dynamic tissue, composed of living bone tissue cells, that undergoes continuous remodeling throughout one’s life to maintain structural integrity, mineral homeostasis, and mechanical function [55,56,57]. This process is tightly regulated by osteoclasts, osteoblasts, and osteocytes. Osteoclasts, derived from monocyte–macrophage lineage precursors, mediate bone resorption, whereas osteoblasts, originating from mesenchymal cells, are responsible for bone matrix synthesis and mineralization [58]. Osteocytes, terminally differentiated from osteoblasts embedded within the mineralized matrix, function as mechanosensors and orchestrators of bone remodeling through paracrine signaling [55,56,57,58].
A central regulatory axis in bone homeostasis is the RANKL–osteoprotegerin (OPG) pathway. RANKL, expressed by osteoblasts, binds to its receptor RANK on osteoclast precursors, promoting their differentiation, activation, and survival. OPG, a receptor secreted by osteoblast lineage cells, antagonizes RANKL and limits osteoclastogenesis [57,59]. The balance between RANKL and OPG is influenced by systemic hormones (such as parathyroid hormone, estrogen and vitamin D) and local cytokines, ensuring coupling between bone resorption and formation [59].
Physiological bone remodeling is further modulated by signaling pathways such as Wnt/β-catenin, transforming growth factor-β (TGF-β), and bone morphogenetic proteins (BMPs), which regulate osteoblast differentiation and activity [60]. The disruption of these finely tuned mechanisms results in pathological bone loss or excessive resorption, as exemplified in GCTB [61].
4. Molecular Biology of Giant Cell Tumor of Bone and Tumorigenesis
GCTB is now recognized as a genetically defined neoplasm driven by recurrent mutations in H3F3A, the gene encoding the histone variant H3.3 [62,63,64]. This discovery reshaped the conceptualization of the tumor from a benign osteoclastic proliferation to a clonal neoplasm of mesenchymal stromal cells [14,15,65,66].
The H3F3A mutation present in most tumors (~90%) consists of p.G34W mutations [30,45,67,68]. Less common mutations are G34V, G34L, G34M, G34R and G34K [45,69,70]. These mutations affect glycine 34, a critical residue near lysine 36 (H3K36), a major regulatory site for transcription, splicing, and chromatin structure [71,72,73]. As a consequence, there is a disruption of the interaction with H3K36 methyltransferase hypomethylation (SETD2), perturbation of the H3K36 landscape, alterations in the transcription of osteoblastic lineage genes, upregulation of RANKL expression, altered nucleosome positioning and the induction of a phenotype resembling defective osteoblastic differentiation [29,73,74].
The aberrant epigenetic state defines the neoplastic stromal cell, the only proliferative cell population in GCTB [50,73,75]. Transcriptomic studies show resemblance to immature osteoblast precursors, limited osteoid production and the absence of terminal osteoblastic markers [44,76,77,78]. These cells orchestrate the recruitment of reactive osteoclast-type giant cells, which constitute the hallmark histological feature but are not neoplastic cells [15,41,44,79].
Neoplastic stromal cells are mononuclear and represent only a small proportion of the total tumor volume, yet they orchestrate the tumor phenotype [15,43,65,79]. These cells originate from mesenchymal stromal lineage; have H3F3A mutations; and secrete high levels of RANKL, colony-stimulating factor 1 (CSF-1) and matrix metalloproteinases (MMPs) that recruit monocytes and promote giant cell formation [42,50,65,66,80]. Their transcriptional profile resembles osteoblastic precursors but with impaired maturation [44,79,81].
Circulating monocytes and tissue-resident macrophages are recruited from the bloodstream and local tissues and differentiate into osteoclast precursors under the influence of CSF-1. These precursor cells are genetically normal and do not exhibit intrinsic molecular alterations [79,82,83,84,85]. Subsequent stimulation by RANKL induces the fusion of monocyte-derived precursors, leading to the formation of multinucleated giant cells that function as mature osteoclasts and are responsible for osteoclastic bone resorption [79,86,87].
As previously described, the H3F3A mutation plays a pivotal role in the pathogenesis of GCTB [5,67,68]. This mutation disrupts normal histone interactions with the epigenetic regulatory machinery, effectively “locking” stromal cells in an undifferentiated progenitor state. This arrested state fosters a permissive microenvironment for osteoclastogenesis, driving the recruitment and activation of osteoclast precursors and contributing to the locally aggressive behavior of the tumor [45,50,65,74,88].
Neoplastic stromal cells in GCTB overproduce RANKL, while osteoprotegerin (OPG), the physiological decoy receptor, is underexpressed. This imbalance drives osteoclast precursor cells, bearing the RANK receptor, to fuse and form multinucleated giant cells, resulting in extensive bone resorption and the locally aggressive nature of the tumor [51,89,90].
GCTB was traditionally treated with surgery, which is often associated with significant morbidity. The introduction of denosumab, a monoclonal antibody that inhibits RANKL, represents a therapeutic advance by allowing for, in many cases, tumor volume reduction and the preservation of anatomical function, with less functional impact [42,91,92]. Denosumab induces histological changes in GCTB. Pharmacological treatment can result in the near-complete elimination of osteoclast-like giant cells and a substantial reduction in the proliferative stromal cell population. These regions are subsequently replaced by dense fibro-osseous tissue and newly formed woven bone, characterized by increased mineral density and a disorganized collagen matrix. Collectively, these findings indicate that denosumab not only suppresses osteoclast-mediated bone resorption but also allows for ossification and structural remodeling within the tumor [13,52,53,93,94,95].
Beyond RANKL inhibition, other molecular factors contribute to tumor behavior: CSF-1 promotes the recruitment and survival of macrophages and osteoclast precursors [84,96,97], while matrix metalloproteinases facilitate local invasion and bone remodeling [98,99,100]. Vascular endothelial growth factor (VEGF) is frequently upregulated, correlating with increased vascular density [101,102,103], and programmed death ligand 1 (PD-L1) expression has been demonstrated, suggesting potential immune checkpoint interactions. Together, these mechanisms underscore the complex microenvironment driving GCTB progression and therapeutic response [104,105,106].
Collectively, these microenvironmental drivers have important therapeutic implications that extend beyond conventional RANKL inhibition. While agents such as denosumab can disrupt osteoclastogenesis, they do not directly target the H3F3A-mutant neoplastic stromal cells or other signaling networks embedded within this pro-tumorigenic niche [64,107]. The persistent activation of pathways involving CSF-1, VEGF, matrix metalloproteinases, and immune checkpoint molecules such as PD-L1 may contribute to residual tumor activity, adaptive resistance, and disease recurrence following treatment withdrawal [101,102,106,108]. These observations provide a biological rationale for emerging therapeutic strategies that integrate osteoclast inhibition with approaches aimed at the epigenetic reprogramming of stromal cells or modulation of tumor–immune interactions. Accordingly, a deeper understanding of how sustained osteoclast suppression reshapes the local epigenetic, vascular, and immune landscape is essential for optimizing treatment sequencing, minimizing long-term risks, and advancing combination therapies in H3F3A-driven giant cell tumor of bone.
5. Pathophysiology: The Osteoclastogenic Microenvironment
GCTB is a paradigmatic example of a neoplasm that manipulates normal bone homeostasis to promote its own local expansion. The tumoral stromal cell drives this process through the pronounced dysregulation of the RANK–RANKL–OPG signaling axis. Neoplastic stromal cells express RANKL at markedly higher levels than normal osteoblasts, producing a local microenvironment that favors osteoclastogenesis and bone destruction [13,77,109,110,111]. Concomitantly, the expression of the decoy receptor OPG is relatively reduced in these lesions, which removes a physiologic brake on RANKL activity and further shifts the balance toward osteoclast differentiation and activation [51,89,90].
Circulating RANK-positive mononuclear precursors are chemoattracted to the tumor microenvironment, where exposure to stromal-derived RANKL (and other supportive factors) drives their differentiation and fusion into large, multinucleated osteoclast-like giant cells that are the histologic hallmark of GCTB [51,89,90]. These reactive giant cells, while not neoplastic themselves, are the principal effectors of the aggressive osteolysis seen in GCTB. Their resorptive activity is mediated by multiple complementary mechanisms: the secretion of the cysteine protease cathepsin K, acidification of resorption lacunae via proton pumps to dissolve mineral, and localized release of MMPs and other proteases that degrade the organic bone matrix. Together with the physical disruption of bone architecture, these processes produce the characteristic expansile lytic lesions and frequently result in cortical thinning, pathologic fracture, and rapid local progression [80,112,113].
The net result is a self-sustaining cycle in which neoplastic stromal cells recruit and activate osteoclast lineage cells that, in turn, create space for continued stromal proliferation and tumor expansion. This pathogenic model has important translational implications: interrupting RANKL-mediated signaling can suppress osteoclast formation and activity and thereby reduce tumoral bone resorption and mass effect. Clinically, this mechanistic insight underpins targeted therapeutic strategies aimed at neutralizing RANKL and modulating the stromal–osteoclast axis.
In addition to neoplastic stromal cells and multinucleated giant cells, intermediary histiocytic mononuclear cells play a key modulatory role within the GCTB microenvironment. These cells actively contribute to tumor-associated osteolysis through the secretion of a broad array of soluble mediators, including pro-osteoclastogenic cytokines such as interleukin-6 (IL-6) and tumor necrosis factor-α (TNF-α); chemotactic and differentiation factors such as macrophage colony-stimulating factor (M-CSF) and chemokine C-C motif ligand 20 (CCL20); and fusion-related molecules, including dendritic cell-specific transmembrane protein (DC-STAMP) [14,15,44,49,114,115]. Collectively, these factors enhance the recruitment, survival, and fusion of osteoclast precursors, reinforcing a self-perpetuating positive feedback loop that sustains excessive osteoclastogenesis and bone resorption.
In this context, the destructive capacity of GCTB is multifactorial and reflects the convergence of several pathogenic mechanisms: (i) direct osteoclastic bone resorption mediated by multinucleated giant cells; (ii) stromal cell-driven osteolysis through sustained RANKL-rich signaling; (iii) the degradation of osteoid and the extracellular matrix via the overexpression of matrix metalloproteinases; and (iv) progressive expansion within cancellous bone leading to cortical thinning, breach, and eventual extension into adjacent soft tissues. These biological processes account for the characteristic radiological appearance of GCTB, which typically manifests as an expansile, lytic, eccentric lesion lacking matrix mineralization [34,116]. Figure 1 shows the mechanisms underlying GCTB, as well as the site of action of denosumab.
Figure 1.
The mechanisms underlying giant cell tumor of bone, as well as the site of action of denosumab. Legend: CCL20, chemokine C-C motif ligand 20; CSF-1, colony-stimulating factor 1; DC-STAMP, dendritic cell-specific transmembrane protein; H3F3A, H3.3 histone A; IL-6, interleukin-6; M-CSF, macrophage colony-stimulating factor; MMPs, matrix metalloproteinases; OPG, osteoprotegerin; RANK, receptor activator of nuclear factor kappa B; RANKL, receptor activator of nuclear factor kappa B ligand; TNF-α, tumor necrosis factor alpha. Parts of this figure were drawn using pictures from Servier Medical Art by Servier (https://smart.servier.com), which is licensed under Attribution 4.0 International (Creative Commons CC BY 4.0).
6. Gross Pathology and Histopathology
Histopathological evaluation is fundamental to the diagnosis of GCTB, as the lesion exhibits a characteristic microscopic appearance but must be carefully distinguished from several giant cell-rich mimics. The pathology reflects the tumor’s biological organization: neoplastic stromal cells drive the recruitment and differentiation of osteoclast-like giant cells, leading to the archetypal morphological pattern.
The histopathological features of GCTB closely mirror its underlying biological organization. Neoplastic stromal cells orchestrate the recruitment, differentiation, and activation of osteoclast lineage cells, resulting in the characteristic giant cell-rich morphology that defines the lesion [15,80]. This intimate interaction between neoplastic and reactive cellular components underpins both the histologic appearance and aggressive osteolytic behavior of GCTB.
Macroscopically, GCTB typically presents as a soft, friable, tan-brown mass, frequently containing areas of hemorrhage and cystic degeneration. The tumor most often arises in the metaphyseal–epiphyseal region of long bones and demonstrates an expansile growth pattern, with the progressive thinning or breach of the cortical bone and extension into adjacent soft tissues in advanced cases [8,16,37]. Tumor margins commonly show irregular penetration of the cortex, producing a characteristic “worm-hole” pattern of cortical erosion that reflects infiltrative local growth [34,117,118].
Histopathological examination remains the diagnostic cornerstone of GCTB [45,119]. At low magnification, the tumor is characterized by sheets of mononuclear stromal cells interspersed with numerous, evenly distributed osteoclast-type multinucleated giant cells, along with prominent hemorrhage and hemosiderin deposition. Notably, there is an absence of osteoid or chondroid matrix production, except in cases previously treated with denosumab, in which reactive bone formation may be observed [49,114]. At higher magnification, the mononuclear stromal cells display oval- to spindle-shaped nuclei, fine chromatin, inconspicuous nucleoli, and minimal cytologic atypia. Mitotic figures are frequently present but typically normal in morphology, consistent with the proliferative yet low-grade nature of the neoplastic stromal population. In contrast, the multinucleated giant cells are non-neoplastic, closely resemble physiologic osteoclasts, and usually contain 20 to 50 uniform nuclei that are morphologically similar to those of the surrounding stromal cells [14,42,49,65,120].
Immunohistochemistry provides valuable support for the diagnosis and differential diagnosis of GCTB. A hallmark feature is strong nuclear positivity for the H3.3 G34W mutant protein, which is restricted to neoplastic stromal cells and serves as a highly specific diagnostic marker [30,62,121]. The expression of special AT-rich sequence-binding protein 2 (SATB2) further supports the osteoblastic lineage of the stromal cells [122,123,124]. Markers such as CD68 and CD163 highlight the histiocytic and osteoclast lineage populations, particularly within the multinucleated giant cells and mononuclear precursors [48,81,125]. The proliferative index, as assessed by Ki-67, is variable but generally moderate, typically ranging from 5% to 20% [120,126,127].
Equally important is the absence of immunoreactivity for markers associated with histologic mimics. Negativity for H3F3B, mouse double minute 2 homolog (MDM2), cytokeratin, and cyclin-dependent kinase 4 (CDK4) assists in excluding chondroblastoma, osteosarcoma, metastatic carcinoma, and low-grade osteosarcoma, respectively [33,128,129,130,131,132]. Given the broad differential diagnosis of giant cell-rich bone lesions, the careful integration of histomorphology, immunohistochemistry, and clinical–radiological correlation is essential for accurate diagnosis.
7. The Management of Giant Cell Tumor of Bone and the Role of Denosumab
The recommended primary treatment for GCTB is surgical resection, whenever feasible, with the aim of achieving durable local control while preserving anatomical integrity and function. Intralesional curettage with or without local adjuvants (high-speed burring, phenol, argon beam coagulation, or polymethylmethacrylate cementation) is preferred for most appendicular lesions [133]. En bloc resection is reserved for select cases with extensive cortical destruction, soft tissue extension, or recurrent disease where intralesional surgery would result in unacceptable recurrence risk [133].
As previously described, denosumab has emerged as an important systemic therapy for GCTB based on its ability to inhibit osteoclast-like giant cells and suppress osteolysis [134]. It is primarily indicated for patients with unresectable tumors, relapsed or recurrent disease after surgery, or situations in which surgical resection would result in severe morbidity [134]. Denosumab leads to a rapid reduction in tumor-associated giant cells and decreased bone resorption and allows for progressive new bone formation [134]. The approved dosing regimen for denosumab in GCTB consists of 120mg administered subcutaneously every 4 weeks, with additional loading doses on days 8 and 15 of the first month [135]. Calcium and vitamin D supplementation is mandatory to reduce the risk of hypocalcemia [135]. While denosumab is effective in disease control, optimal treatment duration remains uncertain. Prolonged therapy has been associated with concerns including rebound hypercalcemia after discontinuation, atypical femoral fractures, osteonecrosis of the jaw, and potential effects on tumor biology [92]. Consequently, treatment with denosumab and associated therapies should be individualized to achieve the maximum tumor control while minimizing treatment-related morbidity and preserving function.
8. Post-Denosumab Histology
Denosumab therapy induces profound and characteristic histopathological alterations in GCTB, substantially modifying its conventional morphology [92,136,137]. By inhibiting RANKL-mediated osteoclastogenesis, denosumab results in a marked depletion or complete absence of multinucleated osteoclast-type giant cells. Concomitantly, there is prominent deposition of newly formed woven bone and osteoid, often arranged in irregular trabeculae, along with the development of sclerotic, matrix-rich areas that may simulate malignant bone-forming tumors, particularly osteosarcoma [94,120,136].
In parallel, the neoplastic stromal cell population undergoes notable phenotypic changes, becoming smaller, more uniform, and cytologically bland, with a reduction in cellularity and proliferative activity. These therapy-induced modifications can obscure the classic histologic features of GCTB and give rise to diagnostic challenges, as the abundant reactive bone formation may closely resemble osteoblastoma or fibro-osseous lesions. Consequently, accurate diagnosis in denosumab-treated cases requires careful correlation with clinical history, radiologic findings, and immunohistochemical confirmation of the underlying GCTB genotype, particularly through the demonstration of H3F3A (H3.3 G34W) mutant protein expression in residual stromal cells [62,67,138].
9. Treatment Algorithm Considerations and Special Scenarios
In most cases, denosumab is utilized as a secondary or adjunctive therapy following local recurrence after initial surgical management [139]. Its use in the neoadjuvant setting remains controversial, being restricted to uncommon scenarios in which tumor downsizing may facilitate the surgery [140].
For giant cell tumors of the spine, particularly vertebral body lesions where surgical resection could be associated with substantial neurological or mechanical morbidity, alternative local control strategies may be considered. Stereotactic body radiotherapy has emerged as a potential option in select cases, offering high-dose conformal radiation with the relative sparing of surrounding critical structures [141], being considered for unresectable vertebral GCTB, residual disease after incomplete surgery, or patients who are not surgical candidates [141]. Although conventional radiotherapy has historically been associated with concerns regarding malignant transformation, these modern techniques appear to offer improved local control with a more favorable safety profile, though long-term data remain limited [142].
A multidisciplinary approach integrating different medical specialties is essential to tailor treatment strategies, particularly in anatomically challenging or recurrent disease, promoting individualized care pathways in GCTB.
10. Conclusions and Perspectives
GCTB is recognized as a molecularly defined neoplasm driven by H3F3A-mutated stromal cells that orchestrate a highly specialized and profoundly osteoclastogenic tumor microenvironment. The identification of the H3.3 G34W mutation has transformed diagnostic practice, enabling discrimination from histologic mimics and establishing GCTB as a mesenchymal neoplasm with osteoblastic differentiation potential.
Neoplastic stromal cells exhibit marked epigenetic dysregulation, aberrant chromatin architecture, and altered transcriptional programs, which collectively result in the sustained overexpression of RANKL and the recruitment, differentiation, and activation of osteoclast lineage cells. The resulting multinucleated giant cells are reactive rather than neoplastic, yet they account for the tumor’s characteristic morphology and its locally aggressive osteolytic behavior.
Histopathology remains the gold standard to confirm the diagnosis, and its interpretation has evolved in the era of targeted therapy. Denosumab remodels the tumor microenvironment by affecting giant cells and inducing reactive bone formation, changes that may mimic osteoid-producing neoplasms and obscure classic histologic features. In this context, accurate diagnosis requires the careful integration of clinical history, radiologic findings, and immunohistochemical confirmation of the underlying H3F3A mutation, particularly in treated or recurrent lesions.
Clinically, GCTB is characterized by locally aggressive bone destruction and a substantial risk of local recurrence while generally maintaining a favorable overall prognosis. Current management includes pharmacological treatment with denosumab, surgical approaches ranging from intralesional curettage to more extensive resection, radiotherapy for specific cases or combined strategies (Figure 2). Denosumab plays an important adjunctive role in tumor downstaging, neoadjuvant therapy, and the management of unresectable disease. Nevertheless, important unanswered questions remain regarding the long-term consequences of RANKL inhibition, including recurrence patterns following treatment cessation, the risk of malignant transformation, and the optimal duration and timing of therapy.
Figure 2.
Clinical decision-making flowchart for suspected giant cell tumor of bone. Legend: CT, computed tomography; H3F3A, H3.3 histone A; MRI, magnetic resonance imaging.
From a decision-making perspective, the use of denosumab requires careful patient selection and risk stratification. Although effective in suppressing osteoclast-mediated bone destruction, denosumab does not eradicate the H3F3A-mutant neoplastic stromal cells that drive tumor biology, which may contribute to disease persistence and recurrence after treatment discontinuation [21,64]. Prolonged exposure has been associated with increased rates of local recurrence following intralesional surgery, while abrupt cessation, particularly in younger patients, may lead to rebound osteoclast activation and hypercalcemia [143]. In addition, denosumab-induced histological changes, such as the depletion of giant cells and formation of woven bone, can obscure residual tumor and complicate both surgical margins and pathological interpretation. Rare but clinically relevant reports of sarcomatous transformation further underscore the importance of close radiological, biochemical, and histopathological monitoring [53,144]. Collectively, these considerations support a multidisciplinary, individualized approach in which treatment duration, sequencing with surgery, and discontinuation strategies are predefined to balance tumor control with long-term safety.
In parallel, accurate diagnosis remains critical given the wide differential spectrum of giant cell-rich bone lesions. Several benign and malignant entities, including aneurysmal bone cyst, chondroblastoma, giant cell-rich osteosarcoma, brown tumor of hyperparathyroidism, and tenosynovial giant cell tumor, may closely mimic GCTB in terms of morphology alone [145]. In this context, the integration of mutation-specific immunohistochemistry, particularly H3F3A G34W, has become an essential diagnostic tool, allowing for the reliable discrimination of GCTB from its mimics. Additional markers such as H3F3B K36M, SATB2, MDM2/CDK4, and cytokeratin provide further practical utility in resolving challenging cases, especially in post-denosumab specimens where treatment-induced histological alterations may obscure classic features [30,45,64,67,68,120]. Incorporating immunohistochemical and molecular markers into routine diagnostic workflows enhances diagnostic precision and supports appropriate therapeutic decision-making.
Future research priorities include elucidating the clonal evolution and intratumoral heterogeneity of neoplastic stromal cells; identifying molecular or histologic biomarkers predictive of recurrence, metastasis, and malignant transformation; defining the long-term safety and biological impact of denosumab; and developing stromal cell-specific targeted therapies beyond RANKL blockade. Particular attention should be directed toward exploiting the epigenetic vulnerabilities created by the H3F3A mutation as potential therapeutic targets. Also, future research should move beyond descriptive molecular profiling toward integrative, data-driven frameworks capable of informing clinical decision-making. In this context, artificial intelligence and machine learning approaches offer particular promise for risk stratification by combining histopathological features, radiologic patterns, and genomic alterations such as H3F3A mutation status [146,147]. Such models could improve the prediction of local recurrence, malignant transformation, and therapeutic response, enabling personalized surveillance and treatment strategies [146,147]. Prospective, multicenter datasets will be essential to validate these approaches and ensure their applicability across diverse populations [146,147].
Based on current molecular and biological evidence, a hypothetical “H3F3A-driven epigenetic therapy model” can be outlined, suggesting that durable disease control in giant cell tumor of bone may require therapeutic strategies that extend beyond osteoclast suppression and directly address the mutant neoplastic stromal compartment. Within this conceptual framework, RANKL inhibition primarily mitigates the downstream mechanisms of bone destruction, whereas future approaches may focus on reversing aberrant chromatin states induced by H3F3A mutations, restoring osteoblastic differentiation programs, or modulating the immune and vascular components of the tumor microenvironment. Epigenetic therapies, stromal-targeted agents, and immune-based interventions could ultimately be integrated with osteoclast inhibition to achieve more sustained biological control. This framework positions giant cell tumor of bone as a prototype of mutation-driven, microenvironment-dependent bone neoplasia and offers a translational rationale for next-generation combination therapeutic strategies [73,148,149].
This narrative review has inherent limitations due to its non-systematic design, which may introduce selection and publication bias and precludes quantitative synthesis; despite the use of a structured search strategy, the predominance of retrospective clinical series and small observational cohorts in the GCTB literature makes the selection and interpretation of studies particularly susceptible to publication and reporting biases. In fact, the available evidence on giant cell tumor of bone is heterogeneous and largely derived from retrospective studies, small clinical series, and experimental models, limiting comparability and generalizability. In addition, the interpretation of histopathologic features, particularly in denosumab-treated lesions, remains partly subjective, and long-term data on recurrence, malignant transformation, and optimal therapeutic strategies are still limited. Future systematic reviews, ideally supported by a more standardized reporting of outcomes, harmonized diagnostic criteria, and prospective multicenter datasets, may be better positioned to reduce these sources of bias, enable more robust comparative analyses, and potentially allow for meaningful quantitative synthesis or meta-analytic approaches. Moreover, future studies should be designed with greater methodological rigor, including well-structured prospective cohorts and, when feasible, randomized controlled trials. Such improvements in study quality would generate more robust and comparable data, ultimately enabling high-quality systematic reviews and meaningful meta-analyses that can better inform clinical practice.
In summary, GCTB lies at the intersection of bone biology, epigenetics, and tumor–microenvironment interactions. Advances in molecular pathology and targeted therapy have markedly improved diagnostic precision and clinical management; however, fully translating biological insights into durable, mechanism-based therapeutic strategies remains an ongoing challenge.
Author Contributions
Conceptualization, B.D.C., C.S.F. and D.H.P.; investigation, B.D.C. and S.B.; imaging, B.D.C. and D.H.P.; writing—original draft preparation, B.D.C. and S.B.; writing—review and editing, B.D.C., S.B., D.H.P., C.S.F. and S.F.; project administration, B.D.C. and D.H.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
All data generated or analyzed during this study are included in the manuscript.
Conflicts of Interest
The authors have no relevant financial or non-financial interests to disclose.
Abbreviations
The following abbreviations are used in this manuscript:
| BMPs | Bone morphogenetic proteins |
| CCL20 | Chemokine C-C motif ligand 20 |
| CD | Cluster of differentiation |
| CD4 | Cyclin-dependent kinase 4 |
| CSF-1 | Colony-stimulating factor 1 |
| CT | Computed tomography |
| DC-STAMP | Dendritic cell-specific transmembrane protein |
| GCTB | Giant cell tumor of bone |
| H3F3A | H3.3 histone A |
| H3F3B | H3.3 histone B |
| IL | Interleukin |
| M-CSF | Macrophage colony-stimulating factor |
| MDM2 | Mouse double minute 2 homolog |
| MMPs | Matrix metalloproteinases |
| MRI | Magnetic resonance imaging |
| OPG | Osteoprotegerin |
| PD-L1 | Programmed death ligand 1 |
| RANK | Receptor activator of nuclear factor kappa B |
| RANKL | Receptor activator of nuclear factor kappa B ligand |
| SATB2 | AT-rich sequence-binding protein 2 |
| SETD2 | H3K36 methyltransferase hypomethylation |
| TNF-α | Tumor necrosis factor alpha |
| TGF-β | Transforming growth factor-β |
| VEGF | Vascular endothelial growth factor |
| WHO | World Health Organization |
Appendix A
Table A1.
Key references of giant cell tumor of bone (GCTB).
References
- Verschoor, A.J.; Bovée, J.; Mastboom, M.J.L.; Sander Dijkstra, P.D.; Van De Sande, M.A.J.; Gelderblom, H. Incidence and demographics of giant cell tumor of bone in The Netherlands: First nationwide Pathology Registry Study. Acta Orthop. 2018, 89, 570–574. [Google Scholar] [CrossRef] [Scilit]
- Liede, A.; Hernandez, R.K.; Tang, E.T.; Li, C.; Bennett, B.; Wong, S.S.; Jandial, D. Epidemiology of benign giant cell tumor of bone in the Chinese population. J. Bone Oncol. 2018, 12, 96–100. [Google Scholar] [CrossRef] [Scilit]
- Liede, A.; Bach, B.A.; Stryker, S.; Hernandez, R.K.; Sobocki, P.; Bennett, B.; Wong, S.S. Regional variation and challenges in estimating the incidence of giant cell tumor of bone. J. Bone Joint Surg. 2014, 96, 1999–2007. [Google Scholar] [CrossRef] [Scilit]
- Amelio, J.M.; Rockberg, J.; Hernandez, R.K.; Sobocki, P.; Stryker, S.; Bach, B.A.; Engellau, J.; Liede, A. Population-based study of giant cell tumor of bone in Sweden (1983–2011). Cancer Epidemiol. 2016, 42, 82–89. [Google Scholar] [CrossRef] [Scilit]
- Leinauer, B.; Wolf, E.; Werner, M.; Baumhoer, D.; Breining, T.; Luebke, A.M.; Maas, R.; Schultheiß, M.; von Baer, A.; Sufi-Siavach, A.; et al. H3F3A-mutated giant cell tumour of bone without giant cells-clinical presentation, radiology and histology of three cases. Histopathology 2021, 79, 720–730. [Google Scholar] [CrossRef] [Scilit]
- Papke, D.J., Jr.; Kovacs, S.K.; Odintsov, I.; Hornick, J.L.; Raskin, K.A.; Newman, E.T.; Lozano-Calderón, S.; Chebib, I.; Hung, Y.P.; Nielsen, G.P. Malignant Giant Cell Tumor of Bone: A Clinicopathologic Series of 28 Cases Highlighting Genetic Differences Compared With Conventional, Atypical, and Metastasizing Conventional Tumors. Am. J. Surg. Pathol. 2025, 49, 539–553. [Google Scholar] [CrossRef] [Scilit]
- Mavrogenis, A.F.; Igoumenou, V.G.; Megaloikonomos, P.D.; Panagopoulos, G.N.; Papagelopoulos, P.J.; Soucacos, P.N. Giant cell tumor of bone revisited. Sicot-J 2017, 3, 54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fellows, D.; Kotowska, J.; Stevenson, T.; Brown, J.; Orosz, Z.; Siddiqi, A.; Whitwell, D.; Cosker, T.; GIbbons, C.L.M.H. Management and surveillance of metastatic giant cell tumour of bone. Pathol. Oncol. Res. 2025, 31, 1611916. [Google Scholar] [CrossRef] [Scilit]
- Deventer, N.; Budny, T.; Gosheger, G.; Rachbauer, A.; Puetzler, J.; Theil, J.C.; Kovtun, D.; de Vaal, M.; Deventer, N. Giant cell tumor of bone: A single center study of 115 cases. J. Bone Oncol. 2022, 33, 100417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jamshidi, K.; Karimi, A.; Mirzaei, A. Epidemiologic Characteristics, Clinical Behavior, and Outcome of the Giant Cell Tumor of the Bone: A Retrospective Single-center Study. Arch. Bone Jt. Surg. 2019, 7, 538–544. [Google Scholar] [PubMed]
- Kumar, I.; Ahmed, W.; Kashyap, N.; Kumar, M.; Saw, M.K.; Shekhar, R. A Retrospective Audit of Demography and Different Surgical Modalities Adopted for Giant Cell Tumor of Bone in Eastern India. Cureus 2022, 14, e29520. [Google Scholar] [CrossRef] [Scilit]
- Howard, E.L.; Gregory, J.; Winn, N.; Flanagan, A.; Cool, P. Radiological Features of Giant Cell Tumours of Bone. Cureus 2020, 12, e8793. [Google Scholar] [CrossRef] [Scilit]
- Hosseinzadeh, S.; Tiwari, V.; De Jesus, O. Giant Cell Tumor (Osteoclastoma). In StatPearls; StatPearls Publishing LLC: Treasure Island, FL, USA, 2025. [Google Scholar]
- Wülling, M.; Engels, C.; Jesse, N.; Werner, M.; Delling, G.; Kaiser, E. The nature of giant cell tumor of bone. J. Cancer Res. Clin. Oncol. 2001, 127, 467–474. [Google Scholar] [CrossRef] [Scilit]
- Werner, M. Giant cell tumour of bone: Morphological, biological and histogenetical aspects. Int. Orthop. 2006, 30, 484–489. [Google Scholar] [CrossRef] [Scilit]
- Haque, A.U.; Moatasim, A. Giant cell tumor of bone: A neoplasm or a reactive condition? Int. J. Clin. Exp. Pathol. 2008, 1, 489–501. [Google Scholar] [PubMed]
- Cheng, J.C.; Johnston, J.O. Giant cell tumor of bone. Prognosis and treatment of pulmonary metastases. Clin. Orthop. Relat. Res. 1997, 338, 205–214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muheremu, A.; Niu, X. Pulmonary metastasis of giant cell tumor of bones. World J. Surg. Oncol. 2014, 12, 261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tubbs, W.S.; Brown, L.R.; Beabout, J.W.; Rock, M.G.; Unni, K.K. Benign giant-cell tumor of bone with pulmonary metastases: Clinical findings and radiologic appearance of metastases in 13 cases. AJR Am. J. Roentgenol. 1992, 158, 331–334. [Google Scholar] [CrossRef] [Scilit]
- Wang, J.; Liu, X.; Yang, Y.; Yang, R.; Tang, X.; Yan, T.; Guo, W. Pulmonary metastasis of giant cell tumour: A retrospective study of three hundred and ten cases. Int. Orthop. 2021, 45, 769–778. [Google Scholar] [CrossRef] [Scilit]
- Tsukamoto, S.; Mavrogenis, A.F.; Kido, A.; Errani, C. Current Concepts in the Treatment of Giant Cell Tumors of Bone. Cancers 2021, 13, 3647. [Google Scholar] [CrossRef] [Scilit]
- WHO Classification of Tumours Editorial Board. Soft Tissue and Bone Tumours; International Agency for Research on Cancer (IARC): Lyon, France, 2020. [Google Scholar]
- Fraquet, N.; Faizon, G.; Rosset, P.; Phillipeau, J.M.; Waast, D.; Gouin, F. Long bones giant cells tumors: Treatment by curretage and cavity filling cementation. Orthop. Traumatol. Surg. Res. 2009, 95, 402–406. [Google Scholar] [CrossRef] [Scilit]
- Leng, A.; Gao, H.; Li, J.; Meng, L.; Wang, Q.; Xiang, L. Intralesional curettage and surgical adjuvants in the treatment of giant cell tumor of bone: Meta-analysis and systematic review. Chin. Clin. Oncol. 2024, 13, 20. [Google Scholar] [CrossRef] [Scilit]
- Abat, F.; Almenara, M.; Peiró, A.; Trullols, L.; Bagué, S.; Grácia, I. Giant cell tumor of bone: A series of 97 cases with a mean follow-up of 12 years. Rev. Española Cirugía Ortopédica Traumatol. (Engl. Ed.) 2015, 59, 59–65. [Google Scholar] [CrossRef] [Scilit]
- Palmerini, E.; Picci, P.; Reichardt, P.; Downey, G. Malignancy in Giant Cell Tumor of Bone: A Review of the Literature. Technol. Cancer Res. Treat. 2019, 18, 1533033819840000. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palmerini, E.; Seeger, L.L.; Gambarotti, M.; Righi, A.; Reichardt, P.; Bukata, S.; Blay, J.Y.; Dai, T.; Jandial, D.; Picci, P. Malignancy in giant cell tumor of bone: Analysis of an open-label phase 2 study of denosumab. BMC Cancer 2021, 21, 89. [Google Scholar] [CrossRef] [Scilit]
- Wang, B.; Chen, W.; Xie, X.; Tu, J.; Huang, G.; Zou, C.; Yin, J.; Wen, L.; Shen, J. Development and validation of a prognostic index to predict pulmonary metastasis of giant cell tumor of bone. Oncotarget 2017, 8, 108054–108063. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamamoto, H.; Ishihara, S.; Toda, Y.; Oda, Y. Histone H3.3 mutation in giant cell tumor of bone: An update in pathology. Med. Mol. Morphol. 2020, 53, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Amary, F.; Berisha, F.; Ye, H.; Gupta, M.; Gutteridge, A.; Baumhoer, D.; Gibbons, R.; Tirabosco, R.; O’Donnell, P.; Flanagan, A.M. H3F3A (Histone 3.3) G34W Immunohistochemistry: A Reliable Marker Defining Benign and Malignant Giant Cell Tumor of Bone. Am. J. Surg. Pathol. 2017, 41, 1059–1068. [Google Scholar] [CrossRef] [Scilit]
- Pasricha, S.; Pruthi, M.; Jajodia, A.; Kumar, A.; Gupta, G.; Sharma, A.; Tiwari, A.; Rohela, H.; Durga, G.; Kamboj, M.; et al. Reliability and Role of Mutation-specific H3F3A (Histone 3-3) G34W Immunohistochemistry to Differentiate Giant Cell Tumor of Bone From its Clinicoradiologic and Histologic Mimics: An Institutional Study. Appl. Immunohistochem. Mol. Morphol. 2022, 30, 36–41. [Google Scholar] [CrossRef] [Scilit]
- Taqi, M.; ul Rasool, H.; Zaka Haider, M.; Al Muderis, M. Significance of Biogenetic Markers in Giant Cell Tumor Differentiation and Prognosis: A Narrative Review. Diagnostics 2025, 15, 39. [Google Scholar] [CrossRef] [Scilit]
- Behjati, S.; Tarpey, P.S.; Presneau, N.; Scheipl, S.; Pillay, N.; Van Loo, P.; Wedge, D.C.; Cooke, S.L.; Gundem, G.; Davies, H.; et al. Distinct H3F3A and H3F3B driver mutations define chondroblastoma and giant cell tumor of bone. Nat. Genet. 2013, 45, 1479–1482, Erratum in Nat. Genet. 2014, 46, 316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Purohit, S.; Pardiwala, D.N. Imaging of giant cell tumor of bone. Indian J. Orthop. 2007, 41, 91–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kelly, D.; Mc Erlean, S.; Byrne, D.; Mahon, P.M.; Mc Caffrey, J. A case of thoracic giant cell tumor of bone and discussion of radiological features and current management practices. Radiol. Case Rep. 2016, 11, 222–226. [Google Scholar] [CrossRef] [Scilit]
- Abbasi, A.N.; Qamar, J.; Habib, A.; Ali, S.M.E.; Ahmed, S.; Khan, M.W. Unraveling the mystery: A comprehensive review of multidisciplinary strategies for managing giant cell tumor of the bone. J. Orthop. Rep. 2025, 4, 100384. [Google Scholar] [CrossRef] [Scilit]
- Sobti, A.; Agrawal, P.; Agarwala, S.; Agarwal, M. Giant Cell Tumor of Bone—An Overview. Arch. Bone Jt. Surg. 2016, 4, 2–9. [Google Scholar]
- Adornato, M.C.; Morcos, I.; Rozanski, J. The treatment of bisphosphonate-associated osteonecrosis of the jaws with bone resection and autologous platelet-derived growth factors. J. Am. Dent. Assoc. 2007, 138, 971–977. [Google Scholar] [CrossRef] [Scilit]
- Vasan, S.; Dhawan, A.; Kaur, T.; Bhullar, R.S.; Kapila, S. Can Tumor Biomarkers Help in Prognostication of Benign Aggressive Lesions of Maxillofacial Region? J. Maxillofac. Oral Surg. 2025, 24, 1378–1385. [Google Scholar] [CrossRef] [Scilit]
- Nelke, K.; Luczak, K.; Janeczek, M.; Plichta, M.; Malyszek, A.; Tarnowska, M.; Kuropka, P.; Dobrzynski, M. The Occurrence of Mandible Brown Tumor Mimicking Central Giant Cell Granuloma in a Case Suspicious of Primary Hyperparathyroidism-Troublesome Diagnostic Dilemmas. Diagnostics 2025, 15, 2038. [Google Scholar] [CrossRef] [Scilit]
- Atkins, G.J.; Haynes, D.R.; Graves, S.E.; Evdokiou, A.; Hay, S.; Bouralexis, S.; Findlay, D.M. Expression of Osteoclast Differentiation Signals by Stromal Elements of Giant Cell Tumors. J. Bone Miner. Res. 2010, 15, 640–649. [Google Scholar] [CrossRef] [Scilit]
- Borkowska, A.M.; Szumera-Ciećkiewicz, A.; Szostakowski, B.; Pieńkowski, A.; Rutkowski, P.L. Denosumab in Giant Cell Tumor of Bone: Multidisciplinary Medical Management Based on Pathophysiological Mechanisms and Real-World Evidence. Cancers 2022, 14, 2290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- López-Pousa, A.; Martín Broto, J.; Garrido, T.; Vázquez, J. Giant cell tumour of bone: New treatments in development. Clin. Transl. Oncol. 2015, 17, 419–430. [Google Scholar] [CrossRef] [Scilit]
- Morgan, T.; Atkins, G.J.; Trivett, M.K.; Johnson, S.A.; Kansara, M.; Schlicht, S.L.; Slavin, J.L.; Simmons, P.; Dickinson, I.; Powell, G.; et al. Molecular profiling of giant cell tumor of bone and the osteoclastic localization of ligand for receptor activator of nuclear factor kappaB. Am. J. Pathol. 2005, 167, 117–128. [Google Scholar] [CrossRef] [Scilit]
- Yao, Y.; Lee, V.K.M.; Chen, E.S. Molecular pathological insights into tumorigenesis and progression of giant cell tumor of bone. J. Bone Oncol. 2025, 51, 100665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hakozaki, M.; Tajino, T.; Yamada, H.; Hasegawa, O.; Tasaki, K.; Watanabe, K.; Konno, S. Radiological and pathological characteristics of giant cell tumor of bone treated with denosumab. Diagn. Pathol. 2014, 9, 111. [Google Scholar] [CrossRef] [Scilit]
- Zhao, C.; Wang, D.; Tang, L.; Zhang, Z.; Li, S.; Qian, M.; Wu, Z.; Zhou, W.; Liu, M.; Luo, J.; et al. Stromal Cell-Derived CCL20 Promotes Tumor Progression and Osteolysis in Giant Cell Tumor of Bone. Cell. Physiol. Biochem. 2018, 51, 2472–2483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hild, V.; Mellert, K.; Möller, P.; Barth, T.F.E. Giant Cells of Various Lesions Are Characterised by Different Expression Patterns of HLA-Molecules and Molecules Involved in the Cell Cycle, Bone Metabolism, and Lineage Affiliation: An Immunohistochemical Study with a Review of the Literature. Cancers 2023, 15, 3702. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, M.H.; Robbins, P.; Xu, J.; Huang, L.; Wood, D.J.; Papadimitriou, J.M. The histogenesis of giant cell tumour of bone: A model of interaction between neoplastic cells and osteoclasts. Histol. Histopathol. 2001, 16, 297–307. [Google Scholar] [CrossRef] [Scilit]
- Noh, B.J.; Park, Y.K. Giant cell tumor of bone: Updated molecular pathogenesis and tumor biology. Hum. Pathol. 2018, 81, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Forsyth, R.G.; Krenács, T.; Athanasou, N.; Hogendoorn, P.C.W. Cell Biology of Giant Cell Tumour of Bone: Crosstalk between m/wt Nucleosome H3.3, Telomeres and Osteoclastogenesis. Cancers 2021, 13, 5119. [Google Scholar] [CrossRef] [Scilit]
- Branstetter, D.G.; Nelson, S.D.; Manivel, J.C.; Blay, J.Y.; Chawla, S.; Thomas, D.M.; Jun, S.; Jacobs, I. Denosumab induces tumor reduction and bone formation in patients with giant-cell tumor of bone. Clin. Cancer Res. 2012, 18, 4415–4424. [Google Scholar] [CrossRef] [Scilit]
- Kumar, R.; Mallya, V.; Mandal, S.; Tomar, R.; Khurana, N.; Maini, L. Histopathological response to denosumab in giant cell tumours of bone—A review of 11 cases. J. Cancer Res. Ther. 2023, 19, 768–772. [Google Scholar] [CrossRef] [Scilit]
- Shi, J.; Sun, X.; Wang, J.; Liang, H.; Liu, X.; Yang, Y.; Tang, X.; Guo, W. Malignant Giant Cell Tumor of Bone: A Study of Clinical, Pathological, and Prognostic Profile from One Single Center. Bioengineering 2025, 12, 911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carneiro, J.; Junqueira, L.C.U. Histologia Básica: Texto, Atlas, 10th ed.; Guanabar-Koogan: Rio de Janeiro, Brazil, 2004. [Google Scholar]
- Silverthorn, D.U. Fisiologia Humana—5.ed.: Uma Abordagem Integrada, 5th ed.; Artmed Editora: Porto Alegre, Brazil, 2009. [Google Scholar]
- Young, B.; O’Dowd, G.; Woodford, P. Wheater’s Functional Histology: A Text and Colour Atlas, 6th ed.; Churchill Livingstone: London, UK, 2014. [Google Scholar]
- Teitelbaum, S.L. Bone resorption by osteoclasts. Science 2000, 289, 1504–1508. [Google Scholar] [CrossRef] [Scilit]
- Boyle, W.J.; Simonet, W.S.; Lacey, D.L. Osteoclast differentiation and activation. Nature 2003, 423, 337–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sims, N.A.; Martin, T.J. Coupling Signals between the Osteoclast and Osteoblast: How are Messages Transmitted between These Temporary Visitors to the Bone Surface? Front. Endocrinol. 2015, 6, 41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Florencio-Silva, R.; Sasso, G.R.; Sasso-Cerri, E.; Simões, M.J.; Cerri, P.S. Biology of Bone Tissue: Structure, Function, and Factors That Influence Bone Cells. BioMed Res. Int. 2015, 2015, 421746. [Google Scholar] [CrossRef] [Scilit]
- Lüke, J.; von Baer, A.; Schreiber, J.; Lübbehüsen, C.; Breining, T.; Mellert, K.; Marienfeld, R.; Schultheiss, M.; Möller, P.; Barth, T.F.E. H3F3A mutation in giant cell tumour of the bone is detected by immunohistochemistry using a monoclonal antibody against the G34W mutated site of the histone H3.3 variant. Histopathology 2017, 71, 125–133. [Google Scholar] [CrossRef] [Scilit]
- Wągrodzki, M.; Tysarowski, A.; Seliga, K.; Wojnowska, A.; Stepaniuk, M.; Castañeda Wysocka, P.; Makuła, D.; Pieńkowski, A.; Szostakowski, B.; Zub, R.; et al. Diagnostic Utility of Genetic and Immunohistochemical H3-3A Mutation Analysis in Giant Cell Tumour of Bone. Int. J. Mol. Sci. 2022, 23, 969. [Google Scholar] [CrossRef] [Scilit]
- Kato, I.; Furuya, M.; Matsuo, K.; Kawabata, Y.; Tanaka, R.; Ohashi, K. Giant cell tumours of bone treated with denosumab: Histological, immunohistochemical and H3F3A mutation analyses. Histopathology 2018, 72, 914–922. [Google Scholar] [CrossRef] [Scilit]
- Parmeggiani, A.; Miceli, M.; Errani, C.; Facchini, G. State of the Art and New Concepts in Giant Cell Tumor of Bone: Imaging Features and Tumor Characteristics. Cancers 2021, 13, 6298. [Google Scholar] [CrossRef] [Scilit]
- Wülling, M.; Delling, G.; Kaiser, E. The origin of the neoplastic stromal cell in giant cell tumor of bone. Hum. Pathol. 2003, 34, 983–993. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Presneau, N.; Baumhoer, D.; Behjati, S.; Pillay, N.; Tarpey, P.; Campbell, P.J.; Jundt, G.; Hamoudi, R.; Wedge, D.C.; Loo, P.V.; et al. Diagnostic value of H3F3A mutations in giant cell tumour of bone compared to osteoclast-rich mimics. J. Pathol. Clin. Res. 2015, 1, 113–123. [Google Scholar] [CrossRef] [Scilit]
- Du, J.; Liu, S.; Miao, L.; Yang, H.; Li, J.; Wang, F.; Wang, X.; Shen, N.; Yang, Z.; Gao, L.; et al. Clinical pathological characteristics correlation of H3F3A gene mutation in giant cell tumor of bone: A study of 96 cases. Transl. Cancer Res. 2025, 14, 4260–4278. [Google Scholar] [CrossRef] [Scilit]
- Gong, L.; Bui, M.M.; Zhang, W.; Sun, X.; Zhang, M.; Yi, D. H3F3A G34 mutation DNA sequencing and G34W immunohistochemistry analysis in 366 cases of giant cell tumors of bone and other bone tumors. Histol. Histopathol. 2021, 36, 61–68. [Google Scholar] [CrossRef] [Scilit]
- Luo, Y.; Tang, J.; Huang, J.; Hu, D.; Bai, Y.; Chen, J.; Sun, K.; Zhang, H.; Liu, Z. Diagnostic value of H3F3A mutation and clinicopathological features of giant cell tumours in non-long bones. J. Bone Oncol. 2023, 38, 100467. [Google Scholar] [CrossRef] [Scilit]
- Khazaei, S.; De Jay, N.; Deshmukh, S.; Hendrikse, L.D.; Jawhar, W.; Chen, C.C.L.; Mikael, L.G.; Faury, D.; Marchione, D.M.; Lanoix, J.; et al. H3.3 G34W Promotes Growth and Impedes Differentiation of Osteoblast-Like Mesenchymal Progenitors in Giant Cell Tumor of Bone. Cancer Discov. 2020, 10, 1968–1987. [Google Scholar] [CrossRef] [Scilit]
- Jain, S.U.; Khazaei, S.; Marchione, D.M.; Lundgren, S.M.; Wang, X.; Weinberg, D.N.; Deshmukh, S.; Juretic, N.; Lu, C.; Allis, C.D.; et al. Histone H3.3 G34 mutations promote aberrant PRC2 activity and drive tumor progression. Proc. Natl. Acad. Sci. USA 2020, 117, 27354–27364. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Venneker, S.; Szuhai, K.; Hogendoorn, P.C.W.; Bovée, J.V.M.G. Mutation-driven epigenetic alterations as a defining hallmark of central cartilaginous tumours, giant cell tumour of bone and chondroblastoma. Virchows Arch. 2020, 476, 135–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lutsik, P.; Baude, A.; Mancarella, D.; Öz, S.; Kühn, A.; Toth, R.; Hey, J.; Toprak, U.H.; Lim, J.; Nguyen, V.H.; et al. Globally altered epigenetic landscape and delayed osteogenic differentiation in H3.3-G34W-mutant giant cell tumor of bone. Nat. Commun. 2020, 11, 5414. [Google Scholar] [CrossRef] [Scilit]
- Venneker, S.; van Eenige, R.; Kruisselbrink, A.B.; Palubeckaitė, I.; Taliento, A.E.; Briaire-de Bruijn, I.H.; Hogendoorn, P.C.W.; van de Sande, M.A.J.; Gelderblom, H.; Mei, H.; et al. Histone Deacetylase Inhibitors as a Therapeutic Strategy to Eliminate Neoplastic “Stromal” Cells from Giant Cell Tumors of Bone. Cancers 2022, 14, 4708. [Google Scholar] [CrossRef] [Scilit]
- Kimura, A.; Toda, Y.; Matsumoto, Y.; Yamamoto, H.; Yahiro, K.; Shimada, E.; Kanahori, M.; Oyama, R.; Fukushima, S.; Nakagawa, M.; et al. Nuclear β-catenin translocation plays a key role in osteoblast differentiation of giant cell tumor of bone. Sci. Rep. 2022, 12, 13438. [Google Scholar] [CrossRef] [Scilit]
- Knechtova, V.; Mahdal, M.; Zambo, I.S.; Skoda, J.; Neradil, J. Biomarkers and therapeutic targets in giant cell tumor of bone: A comprehensive review. Bone 2025, 199, 117566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Steensma, M.R.; Tyler, W.K.; Shaber, A.G.; Goldring, S.R.; Ross, F.P.; Williams, B.O.; Healey, J.H.; Purdue, P.E. Targeting the Giant Cell Tumor Stromal Cell: Functional Characterization and a Novel Therapeutic Strategy. PLoS ONE 2013, 8, e69101. [Google Scholar] [CrossRef] [Scilit]
- Kim, Y.; Nizami, S.; Goto, H.; Lee, F.Y. Modern interpretation of giant cell tumor of bone: Predominantly osteoclastogenic stromal tumor. Clin. Orthop. Surg. 2012, 4, 107–116. [Google Scholar] [CrossRef] [Scilit]
- Cowan, R.W.; Singh, G. Giant cell tumor of bone: A basic science perspective. Bone 2013, 52, 238–246. [Google Scholar] [CrossRef] [Scilit]
- Salerno, M.; Avnet, S.; Alberghini, M.; Giunti, A.; Baldini, N. Histogenetic characterization of giant cell tumor of bone. Clin Orthop. Relat. Res. 2008, 466, 2081–2091. [Google Scholar] [CrossRef] [Scilit]
- Brown, H.K.; Schiavone, K.; Gouin, F.; Heymann, M.-F.; Heymann, D. Biology of Bone Sarcomas and New Therapeutic Developments. Calcif. Tissue Int. 2018, 102, 174–195. [Google Scholar] [CrossRef] [Scilit]
- Lampiasi, N.; Russo, R.; Zito, F. The Alternative Faces of Macrophage Generate Osteoclasts. BioMed Res. Int. 2016, 2016, 9089610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cecchini, M.G.; Hofstetter, W.; Halasy, J.; Wetterwald, A.; Felix, R. Role of CSF-1 in bone and bone marrow development. Mol. Reprod. Dev. 1997, 46, 75–83; discussion 83–84. [Google Scholar] [CrossRef] [PubMed]
- Pereira, M.; Petretto, E.; Gordon, S.; Bassett, J.H.D.; Williams, G.R.; Behmoaras, J. Common signalling pathways in macrophage and osteoclast multinucleation. J. Cell Sci. 2018, 131, jcs216267. [Google Scholar] [CrossRef] [Scilit]
- Wu, P.F.; Tang, J.Y.; Li, K.H. RANK pathway in giant cell tumor of bone: Pathogenesis and therapeutic aspects. Tumour. Biol. 2015, 36, 495–501. [Google Scholar] [CrossRef] [Scilit]
- Huang, X.-L.; Liu, C.; Shi, X.-M.; Cheng, Y.-T.; Zhou, Q.; Li, J.-P.; Liao, J. Zoledronic acid inhibits osteoclastogenesis and bone resorptive function by suppressing RANKL-mediated NF-κB and JNK and their downstream signalling pathways. Mol. Med. Rep. 2022, 25, 59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cottone, L.; Ligammari, L.; Lee, H.-M.; Knowles, H.J.; Henderson, S.; Bianco, S.; Davies, C.; Strauss, S.; Amary, F.; Leite, A.P.; et al. Aberrant paracrine signalling for bone remodelling underlies the mutant histone-driven giant cell tumour of bone. Cell Death Differ. 2022, 29, 2459–2471. [Google Scholar] [CrossRef] [Scilit]
- Huang, L.; Xu, J.; Wood, D.J.; Zheng, M.H. Gene expression of osteoprotegerin ligand, osteoprotegerin, and receptor activator of NF-kappaB in giant cell tumor of bone: Possible involvement in tumor cell-induced osteoclast-like cell formation. Am. J. Pathol. 2000, 156, 761–767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dufresne, A.; Derbel, O.; Cassier, P.; Vaz, G.; Decouvelaere, A.V.; Blay, J.Y. Giant-cell tumor of bone, anti-RANKL therapy. Bonekey Rep. 2012, 1, 149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gupta, A.; Durocher-Allen, L.; Popovic, S.; Tozer, R.; Yao, X.; Ghert, M. The Role of Denosumab for Surgical Outcomes in Patients with Giant Cell Tumour of Bone: A Systematic Review. Curr. Oncol. 2021, 28, 1302–1313. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Gao, J.; Gao, Y.; Lin, N.; Zheng, M.; Ye, Z. Denosumab in Giant Cell Tumor of Bone: Current Status and Pitfalls. Front. Oncol. 2020, 10, 580605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, S.F.; Adams, B.; Yu, X.C.; Xu, M. Denosumab and giant cell tumour of bone-a review and future management considerations. Curr. Oncol. 2013, 20, e442–e447. [Google Scholar] [CrossRef] [Scilit]
- Birch, R.; Eltit, F.; Xie, D.; Wang, Q.; Dea, N.; Fisher, C.G.; Cox, M.E.; Ng, T.; Charest-Morin, R.; Wang, R. Denosumab treatment of giant cell tumors in the spine induces woven bone formation. JBMR Plus 2025, 9, ziaf063. [Google Scholar] [CrossRef] [Scilit]
- Noguchi, T.; Sakamoto, A.; Murotani, Y.; Murata, K.; Hirata, M.; Yamada, Y.; Toguchida, J.; Matsuda, S. Inhibition of RANKL Expression in Osteocyte-like Differentiated Tumor Cells in Giant Cell Tumor of Bone After Denosumab Treatment. J. Histochem. Cytochem. 2023, 71, 131–138. [Google Scholar] [CrossRef] [Scilit]
- Fujikawa, Y.; Sabokbar, A.; Neale, S.D.; Itonaga, I.; Torisu, T.; Athanasou, N.A. The effect of macrophage-colony stimulating factor and other humoral factors (interleukin-1, -3, -6, and -11, tumor necrosis factor-alpha, and granulocyte macrophage-colony stimulating factor) on human osteoclast formation from circulating cells. Bone 2001, 28, 261–267. [Google Scholar] [CrossRef] [Scilit]
- Kitaura, H.; Marahleh, A.; Ohori, F.; Noguchi, T.; Shen, W.-R.; Qi, J.; Nara, Y.; Pramusita, A.; Kinjo, R.; Mizoguchi, I. Osteocyte-Related Cytokines Regulate Osteoclast Formation and Bone Resorption. Int. J. Mol. Sci. 2020, 21, 5169. [Google Scholar] [CrossRef] [Scilit]
- Zhou, X.; Liu, X.Z.; Fan, G.T.; Wu, S.J.; Zhao, J.N.; Shi, X. Expression of Matrix Metalloproteinase-9 and CD34 in Giant Cell Tumor of Bone. Orthop. Surg. 2016, 8, 220–225. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mak, I.W.; Cowan, R.W.; Popovic, S.; Colterjohn, N.; Singh, G.; Ghert, M. Upregulation of MMP-13 via Runx2 in the stromal cell of Giant Cell Tumor of bone. Bone 2009, 45, 377–386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brown, G.T.; Murray, G.I. Current mechanistic insights into the roles of matrix metalloproteinases in tumour invasion and metastasis. J. Pathol. 2015, 237, 273–281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, M.H.; Xu, J.; Robbins, P.; Pavlos, N.; Wysocki, S.; Kumta, S.M.; Wood, D.J.; Papadimitriou, J.M. Gene expression of vascular endothelial growth factor in giant cell tumors of bone. Hum. Pathol. 2000, 31, 804–812. [Google Scholar] [CrossRef] [Scilit]
- Kumta, S.M.; Huang, L.; Cheng, Y.Y.; Chow, L.T.; Lee, K.M.; Zheng, M.H. Expression of VEGF and MMP-9 in giant cell tumor of bone and other osteolytic lesions. Life Sci. 2003, 73, 1427–1436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feleke, M.; Feng, W.; Song, D.; Li, H.; Rothzerg, E.; Wei, Q.; Kõks, S.; Wood, D.; Liu, Y.; Xu, J. Single-cell RNA sequencing reveals differential expression of EGFL7 and VEGF in giant-cell tumor of bone and osteosarcoma. Exp. Biol. Med. 2022, 247, 1214–1227. [Google Scholar] [CrossRef] [Scilit]
- Metovic, J.; Annaratone, L.; Linari, A.; Osella-Abate, S.; Musuraca, C.; Veneziano, F.; Vignale, C.; Bertero, L.; Cassoni, P.; Ratto, N.; et al. Prognostic role of PD-L1 and immune-related gene expression profiles in giant cell tumors of bone. Cancer Immunol. Immunother. 2020, 69, 1905–1916. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toda, Y.; Kohashi, K.; Yamamoto, H.; Ishihara, S.; Ito, Y.; Susuki, Y.; Kawaguchi, K.; Kiyozawa, D.; Takamatsu, D.; Kinoshita, I.; et al. Tumor microenvironment in giant cell tumor of bone: Evaluation of PD-L1 expression and SIRPα infiltration after denosumab treatment. Sci. Rep. 2021, 11, 14821. [Google Scholar] [CrossRef] [Scilit]
- Hashimoto, K.; Nishimura, S.; Goto, K. PD-1/PD-L1 immune checkpoint in bone and soft tissue tumors (Review). Mol. Clin. Oncol. 2025, 22, 31. [Google Scholar] [CrossRef] [Scilit]
- Wessel, L.E.; Strike, S.A.; Singh, A.; Bernthal, N.M.; Athanasian, E.A. The Role of Denosumab in the Treatment of Primary Tumors of Bone. J. Hand Surg. Am. 2023, 48, 923–930. [Google Scholar] [CrossRef] [Scilit]
- Zheng, B.; Yu, L.; Hu, J.; Xu, H.; Wang, J.; Shi, Y.; Luo, X.; Yan, W. Expression of PD-L1 in mononuclear cells, multinucleated cells, and foam cells in tenosynovial giant cell tumors. Int. J. Clin. Exp. Pathol. 2019, 12, 876–884. [Google Scholar] [PubMed]
- Won, K.Y.; Kalil, R.K.; Kim, Y.W.; Park, Y.K. RANK signalling in bone lesions with osteoclast-like giant cells. Pathology 2011, 43, 318–321. [Google Scholar] [CrossRef] [Scilit]
- Roux, S.; Amazit, L.; Meduri, G.; Guiochon-Mantel, A.; Milgrom, E.; Mariette, X. RANK (receptor activator of nuclear factor kappa B) and RANK ligand are expressed in giant cell tumors of bone. Am. J. Clin. Pathol. 2002, 117, 210–216. [Google Scholar] [CrossRef] [Scilit]
- Peters, S.; Clézardin, P.; Márquez-Rodas, I.; Niepel, D.; Gedye, C. The RANK–RANKL axis: An opportunity for drug repurposing in cancer? Clin. Transl. Oncol. 2019, 21, 977–991. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lindeman, J.H.; Hanemaaijer, R.; Mulder, A.; Dijkstra, P.D.; Szuhai, K.; Bromme, D.; Verheijen, J.H.; Hogendoorn, P.C. Cathepsin K is the principal protease in giant cell tumor of bone. Am. J. Pathol. 2004, 165, 593–600. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahmadzadeh, K.; Vanoppen, M.; Rose, C.D.; Matthys, P.; Wouters, C.H. Multinucleated Giant Cells: Current Insights in Phenotype, Biological Activities, and Mechanism of Formation. Front. Cell Dev. Biol. 2022, 10, 873226. [Google Scholar] [CrossRef] [Scilit]
- van der Heijden, L.; Dijkstra, P.D.S.; Blay, J.Y.; Gelderblom, H. Giant cell tumour of bone in the denosumab era. Eur. J. Cancer 2017, 77, 75–83. [Google Scholar] [CrossRef] [Scilit]
- Yagi, M.; Miyamoto, T.; Sawatani, Y.; Iwamoto, K.; Hosogane, N.; Fujita, N.; Morita, K.; Ninomiya, K.; Suzuki, T.; Miyamoto, K.; et al. DC-STAMP is essential for cell-cell fusion in osteoclasts and foreign body giant cells. J. Exp. Med. 2005, 202, 345–351. [Google Scholar] [CrossRef] [Scilit]
- Chakarun, C.J.; Forrester, D.M.; Gottsegen, C.J.; Patel, D.B.; White, E.A.; Matcuk, G.R., Jr. Giant cell tumor of bone: Review, mimics, and new developments in treatment. Radiographics 2013, 33, 197–211. [Google Scholar] [CrossRef] [Scilit]
- Ali, N.; Shah, A.A.; Rakshan, I. Clinical Scenario and Imaging with Illustrations of Giant Cell Tumor of Bone: A Retrospective Analysis. Arch. Bone Jt. Surg. 2022, 10, 60–66. [Google Scholar] [CrossRef] [Scilit]
- Wang, H.; Wan, N.; Hu, Y. Giant cell tumour of bone: A new evaluating system is necessary. Int. Orthop. 2012, 36, 2521–2527. [Google Scholar] [CrossRef] [Scilit]
- Çomunoğlu, N.; Kepil, N.; Dervişoğlu, S. Histopathology of giant cell tumors of the bone: With special emphasis on fibrohistiocytic and aneurysmal bone cyst like components. Acta Orthop. Traumatol. Turc. 2019, 53, 35–39. [Google Scholar] [CrossRef] [Scilit]
- Arndt, S.; Hartmann, W.; Rókusz, A.; Leinauer, B.; von Baer, A.; Schultheiss, M.; Pablik, J.; Fritzsche, H.; Mogler, C.; Antal, I.; et al. Histomorphometric Analysis of 38 Giant Cell Tumors of Bone after Recurrence as Compared to Changes Following Denosumab Treatment. Cancers 2023, 15, 4249. [Google Scholar] [CrossRef] [Scilit]
- Rekhi, B.; Dave, V.; Butle, A.; Dharavath, B.; Khetale, S.; Redhu, A.K.; Singh, R.; Dutt, A. Immunohistochemical expression of H3.3 G34W in 100 giant cell tumors of bone and its diagnostic mimics, including its value in resolving uncommon diagnostic scenarios: A single institutional study at a tertiary cancer referral center, India. Indian J. Pathol. Microbiol. 2024, 67, 542–552. [Google Scholar] [CrossRef] [Scilit]
- Conner, J.R.; Hornick, J.L. SATB2 is a novel marker of osteoblastic differentiation in bone and soft tissue tumours. Histopathology 2013, 63, 36–49. [Google Scholar] [CrossRef] [Scilit]
- Kerr, D.A.; Brcic, I.; Diaz-Perez, J.A.; Shih, A.; Wilky, B.A.; Pretell-Mazzini, J.; Subhawong, T.K.; Nielsen, G.P.; Rosenberg, A.E. Immunohistochemical Characterization of Giant Cell Tumor of Bone Treated With Denosumab: Support for Osteoblastic Differentiation. Am. J. Surg. Pathol. 2021, 45, 93–100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, J.; Tu, Q.; Grosschedl, R.; Kim, M.S.; Griffin, T.; Drissi, H.; Yang, P.; Chen, J. Roles of SATB2 in osteogenic differentiation and bone regeneration. Tissue Eng. Part A 2011, 17, 1767–1776. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Masui, F.; Ushigome, S.; Fujii, K. Giant cell tumor of bone: An immunohistochemical comparative study. Pathol. Int. 1998, 48, 355–361. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ismail, F.W.; Shamsudin, A.M.; Wan, Z.; Daud, S.M.; Samarendra, M.S. Ki-67 immuno-histochemistry index in stage III giant cell tumor of the bone. J. Exp. Clin. Cancer Res. 2010, 29, 25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sulh, M.A.; Greco, M.A.; Jiang, T.; Goswami, S.B.; Present, D.; Steiner, G. Proliferation index and vascular density of giant cell tumors of bone: Are they prognostic markers? Cancer 1996, 77, 2044–2051. [Google Scholar] [CrossRef] [Scilit]
- Hazell, G.G.; Peachey, A.M.; Teasdale, J.E.; Sala-Newby, G.B.; Angelini, G.D.; Newby, A.C.; White, S.J. PI16 is a shear stress and inflammation-regulated inhibitor of MMP2. Sci. Rep. 2016, 6, 39553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kervarrec, T.; Collin, C.; Larousserie, F.; Bouvier, C.; Aubert, S.; Gomez-Brouchet, A.; Marie, B.; Miquelestorena-Standley, E.; Le Nail, L.R.; Avril, P.; et al. H3F3 mutation status of giant cell tumors of the bone, chondroblastomas and their mimics: A combined high resolution melting and pyrosequencing approach. Mod. Pathol. 2017, 30, 393–406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dujardin, F.; Binh, M.B.N.; Bouvier, C.; Gomez-Brouchet, A.; Larousserie, F.; Muret, A.d.; Louis-Brennetot, C.; Aurias, A.; Coindre, J.-M.; Guillou, L.; et al. MDM2 and CDK4 immunohistochemistry is a valuable tool in the differential diagnosis of low-grade osteosarcomas and other primary fibro-osseous lesions of the bone. Modern Pathology 2011, 24, 624–637. [Google Scholar] [CrossRef] [Scilit]
- Selves, J.; Long-Mira, E.; Mathieu, M.C.; Rochaix, P.; Ilié, M. Immunohistochemistry for Diagnosis of Metastatic Carcinomas of Unknown Primary Site. Cancers 2018, 10, 108. [Google Scholar] [CrossRef] [Scilit]
- Murtaza, H.; Arain, A.R.; Anoushiravani, A.; Thadani, S.; de la Roza, G.; Naous, R.; Damron, T.A. Cytokeratin-Positive Osteosarcoma Simulating Sarcomatoid Metastatic Carcinoma. Case Rep. Orthop. 2020, 2020, 3761015. [Google Scholar] [CrossRef] [Scilit]
- Campanacci, M.; Baldini, N.; Boriani, S.; Sudanese, A. Giant-cell tumor of bone. J. Bone Jt. Surg. 1987, 69, 106–114. [Google Scholar] [CrossRef] [Scilit]
- Thomas, D.; Henshaw, R.; Skubitz, K.; Chawla, S.; Staddon, A.; Blay, J.Y.; Roudier, M.; Smith, J.; Ye, Z.; Sohn, W.; et al. Denosumab in patients with giant-cell tumour of bone: An open-label, phase 2 study. Lancet Oncol. 2010, 11, 275–280. [Google Scholar] [CrossRef] [Scilit]
- Chawla, S.; Blay, J.Y.; Rutkowski, P.; Le Cesne, A.; Reichardt, P.; Gelderblom, H.; Grimer, R.J.; Choy, E.; Skubitz, K.; Seeger, L.; et al. Denosumab in patients with giant-cell tumour of bone: A multicentre, open-label, phase 2 study. Lancet Oncol. 2019, 20, 1719–1729. [Google Scholar] [CrossRef] [Scilit]
- Tariq, M.U.; Umer, M.; Khan, Z.; Saeed, J.; Siddiqui, M.A.; Din, N.U. Spectrum of histological features of Denosumab treated Giant Cell Tumor of Bone; potential pitfalls and diagnostic challenges for pathologists. Ann. Diagn. Pathol. 2020, 45, 151479. [Google Scholar] [CrossRef] [Scilit]
- Wojcik, J.; Rosenberg, A.E.; Bredella, M.A.; Choy, E.; Hornicek, F.J.; Nielsen, G.P.; Deshpande, V. Denosumab-treated Giant Cell Tumor of Bone Exhibits Morphologic Overlap With Malignant Giant Cell Tumor of Bone. Am. J. Surg. Pathol. 2016, 40, 72–80. [Google Scholar] [CrossRef] [Scilit]
- Hasenfratz, M.; Mellert, K.; Marienfeld, R.; von Baer, A.; Schultheiss, M.; Roitman, P.D.; Aponte-Tinao, L.A.; Lehner, B.; Möller, P.; Mechtersheimer, G.; et al. Profiling of three H3F3A-mutated and denosumab-treated giant cell tumors of bone points to diverging pathways during progression and malignant transformation. Sci. Rep. 2021, 11, 5709. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Errani, C.; Tsukamoto, S.; Leone, G.; Righi, A.; Akahane, M.; Tanaka, Y.; Donati, D.M. Denosumab May Increase the Risk of Local Recurrence in Patients with Giant-Cell Tumor of Bone Treated with Curettage. J. Bone Jt. Surg. 2018, 100, 496–504. [Google Scholar] [CrossRef] [Scilit]
- Rutkowski, P.; Ferrari, S.; Grimer, R.J.; Stalley, P.D.; Dijkstra, S.P.; Pienkowski, A.; Vaz, G.; Wunder, J.S.; Seeger, L.L.; Feng, A.; et al. Surgical downstaging in an open-label phase II trial of denosumab in patients with giant cell tumor of bone. Ann. Surg. Oncol. 2015, 22, 2860–2868. [Google Scholar] [CrossRef] [Scilit]
- Shi, W.; Indelicato, D.J.; Reith, J.; Smith, K.B.; Morris, C.G.; Scarborough, M.T.; Gibbs, C.P., Jr.; Mendenhall, W.M.; Zlotecki, R.A. Radiotherapy in the management of giant cell tumor of bone. Am. J. Clin. Oncol. 2013, 36, 505–508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hwang, L.; Okoye, C.C.; Patel, R.B.; Sahgal, A.; Foote, M.; Redmond, K.J.; Hofstetter, C.; Saigal, R.; Mossa-Basha, M.; Yuh, W.; et al. Stereotactic body radiotherapy for benign spinal tumors: Meningiomas, schwannomas, and neurofibromas. J. Radiosurg. SBRT 2019, 6, 167–177. [Google Scholar] [PubMed]
- Liu, D.; Chen, J.; Chen, H.; Hu, W.; Lin, J. Rebound Hypercalcemia After Denosumab Cessation in Adult Fibrous Dysplasia: A Case Report and Clinical Alert. Case Rep. Endocrinol. 2025, 2025, 4553039. [Google Scholar] [CrossRef] [Scilit]
- Gilani, A.; Kleinschmidt-DeMasters, B.K. Denosumab Therapy Obscures Histological Features of Giant Cell Tumor of Bone. J. Neuropathol. Exp. Neurol. 2019, 78, 1171–1173. [Google Scholar] [CrossRef] [Scilit]
- Macagno, N.; Caselles, K.; Aubert, S.; Audard, V.; Gomez-Brouchet, A.; Galant, C.; Guinebretiere, J.M.; Karanian, M.; Larousserie, F.; Marie, B.; et al. Benign and malignant giant-cell rich lesions of bone: Pathological diagnosis with special emphasis on recent immunohistochemistry and molecular techniques. Ann. Pathol. 2018, 38, 92–102. [Google Scholar] [CrossRef] [Scilit]
- Takamatsu, M. Transforming histologic assessment: Artificial intelligence in cancer diagnosis and personalized treatment. Br. J. Cancer 2025, 133, 1765–1775, Erratum in Br. J. Cancer 2025, 133, 1926. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shmatko, A.; Ghaffari Laleh, N.; Gerstung, M.; Kather, J.N. Artificial intelligence in histopathology: Enhancing cancer research and clinical oncology. Nat. Cancer 2022, 3, 1026–1038. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marei, H.E. Epigenetic regulators in cancer therapy and progression. NPJ Precis. Oncol. 2025, 9, 206. [Google Scholar] [CrossRef] [Scilit]
- Wu, W.; Cui, Y.; Wu, Y.; Ni, Y.; Zhao, C.; Sun, W.; Yi, Q. Epigenetic roles of chromatin remodeling complexes in bone biology and the pathogenesis of bone-related disease (Review). Int. J. Mol. Med. 2025, 56, 115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
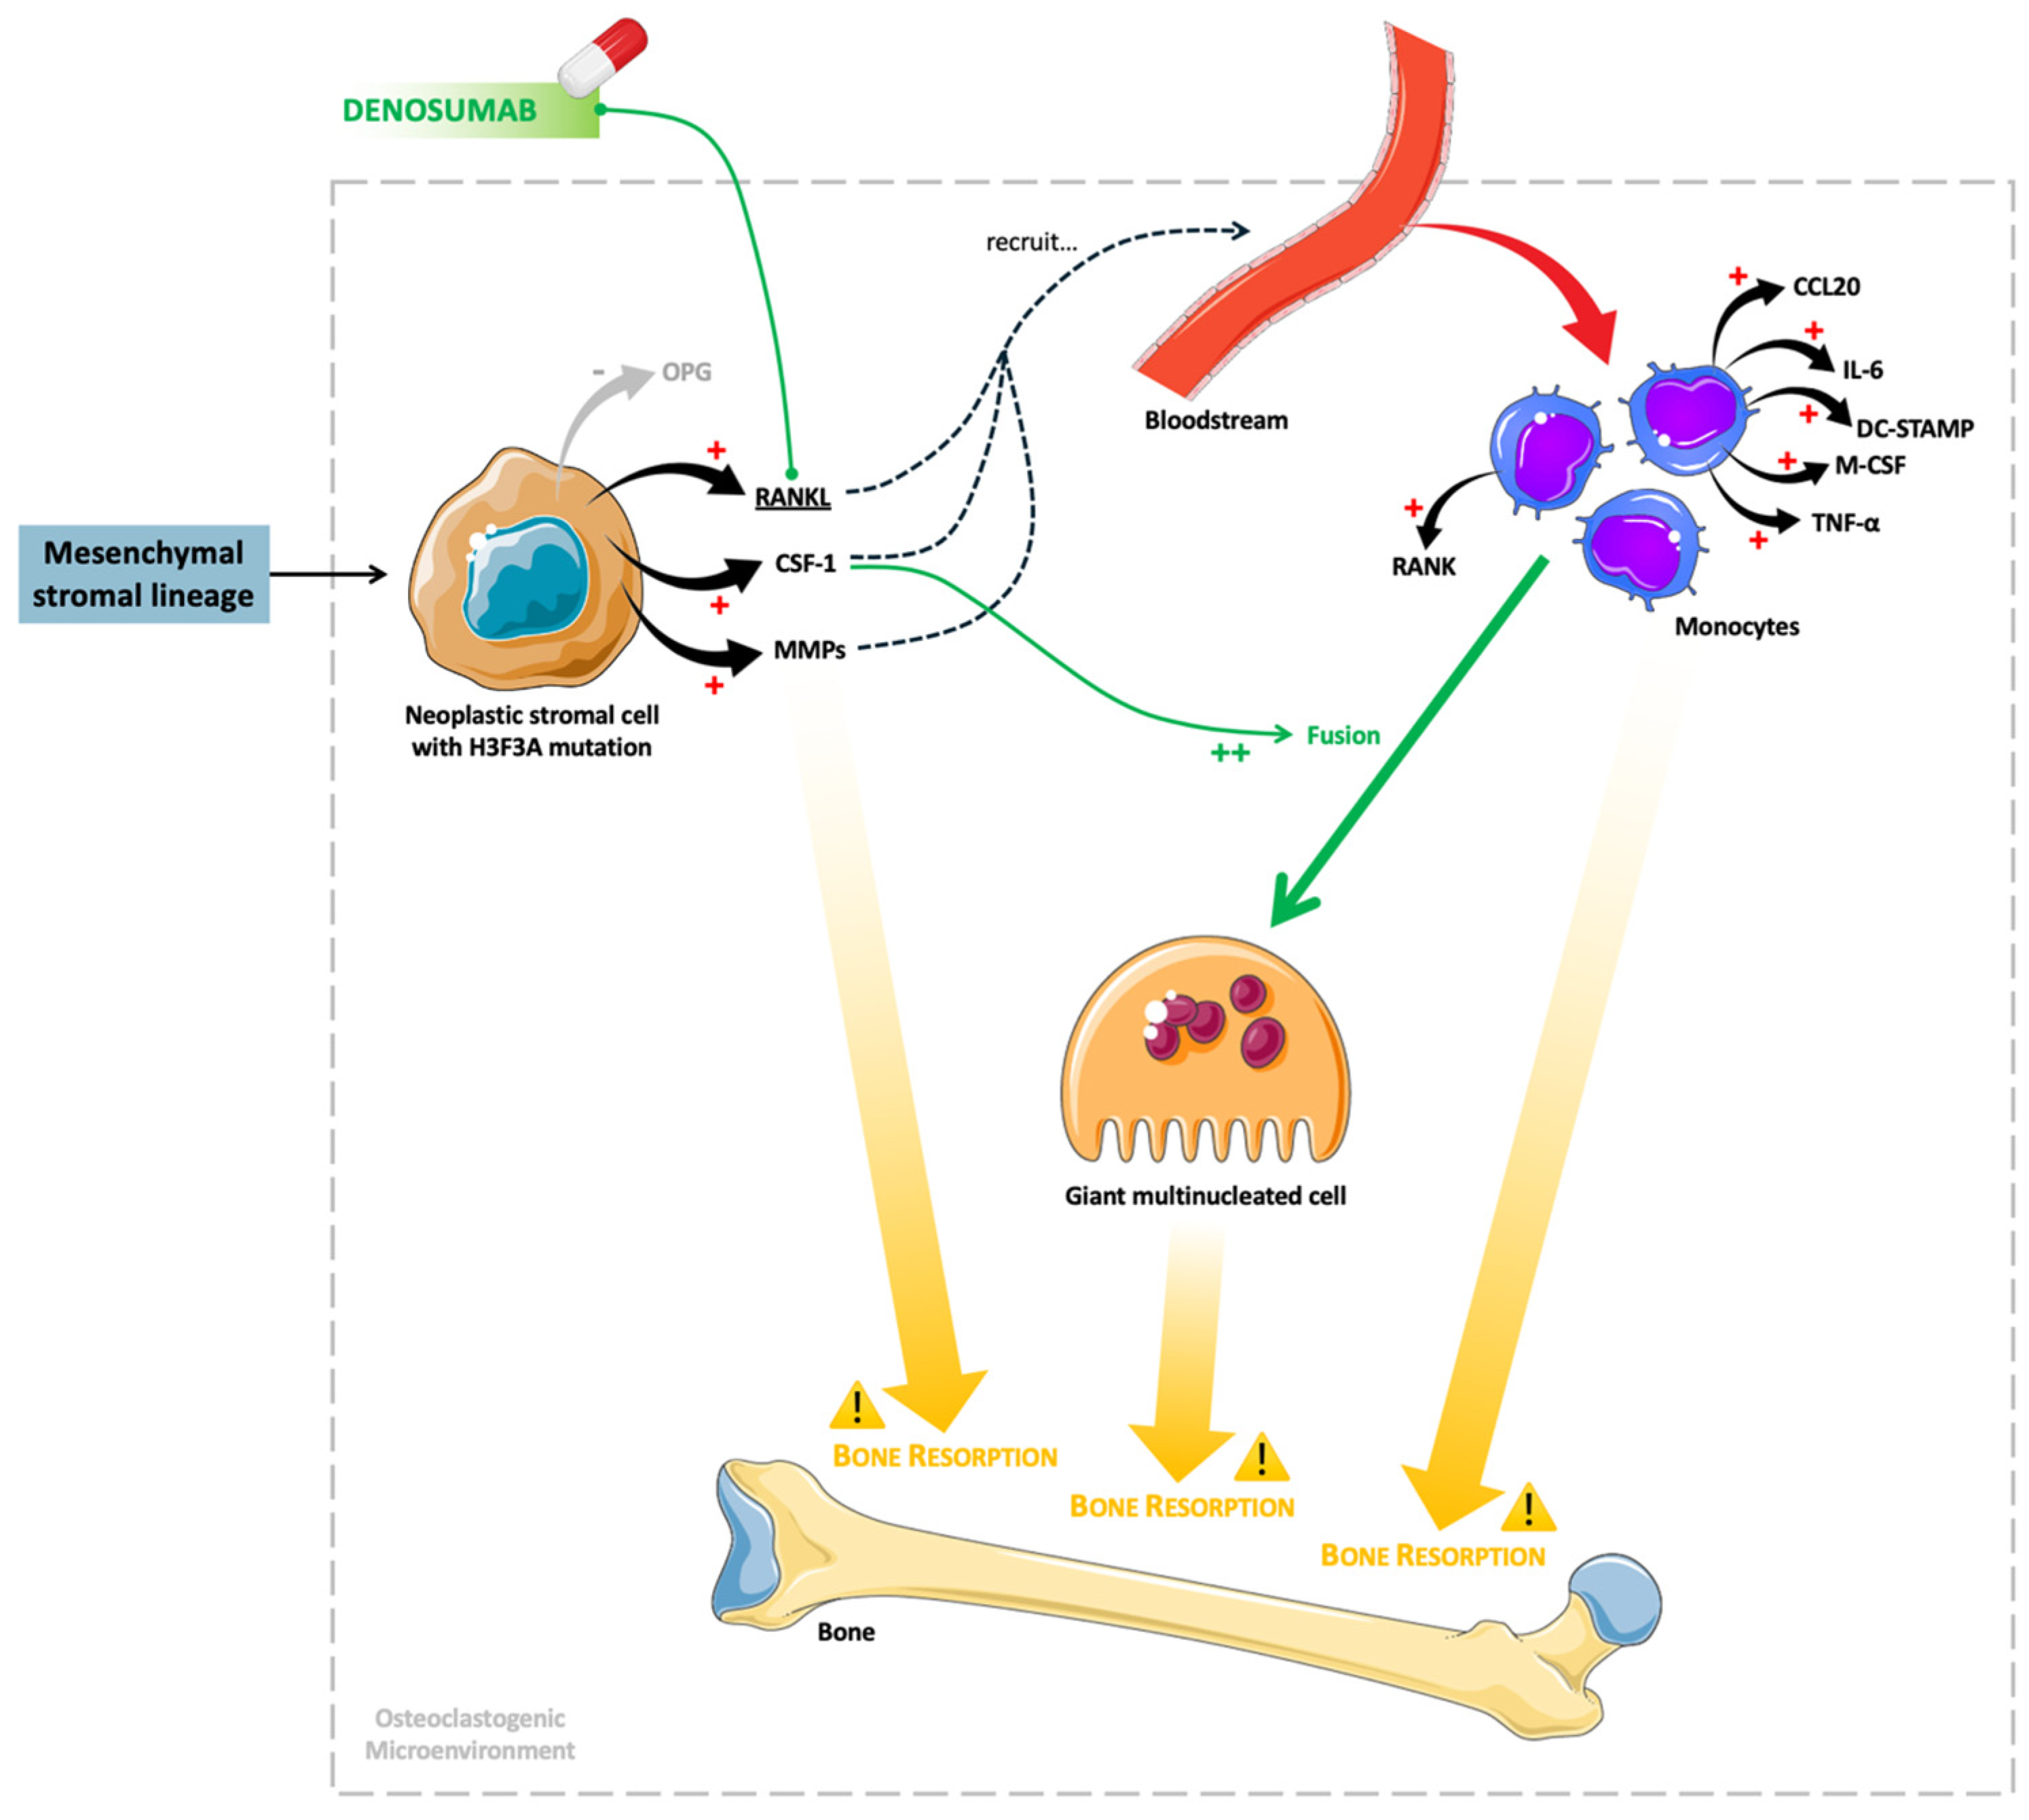
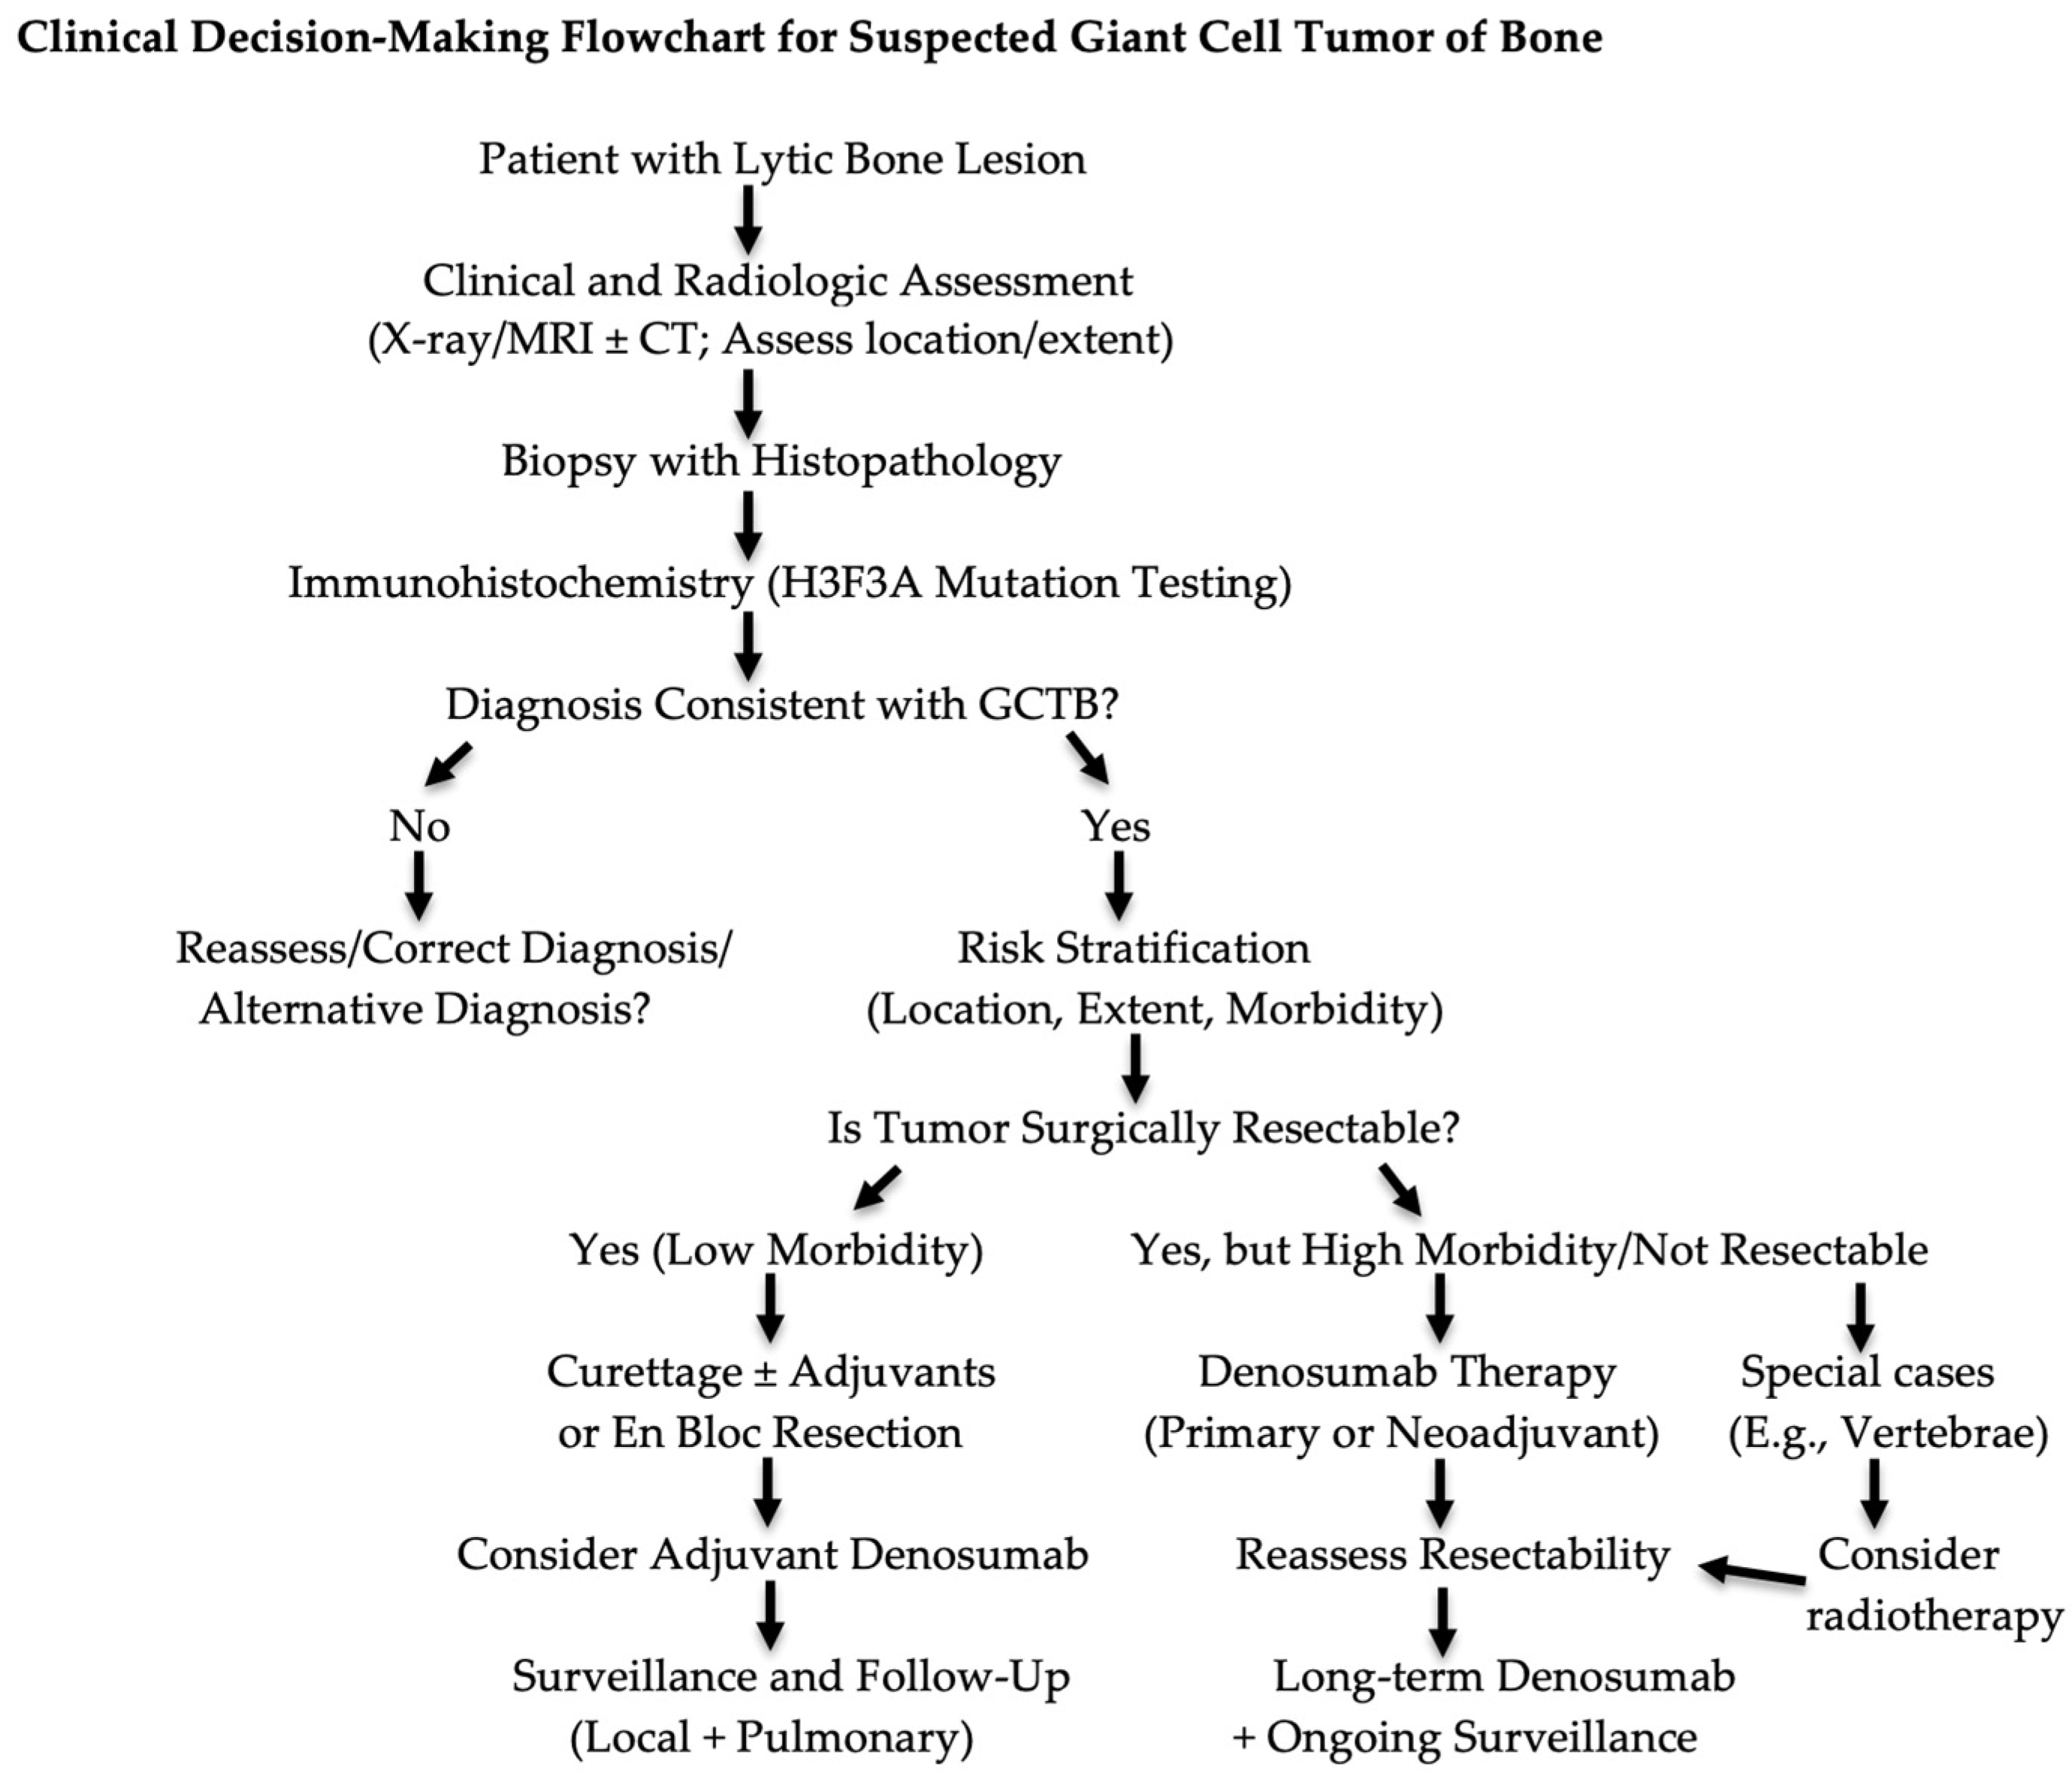
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.