Skip to Content
  • 27 days
    Submission to First Decision
  • 5 days
    Acceptance to Publication

Journal of Otorhinolaryngology, Hearing and Balance Medicine

Journal of Otorhinolaryngology, Hearing and Balance Medicine is an international, scientific, peer-reviewed, open access journal of otorhinolaryngology, hearing and balance medical studies, published semiannually online by MDPI.
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 26.2 days after submission; acceptance to publication is undertaken in 4.6 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (121)

  • Review
  • Open Access

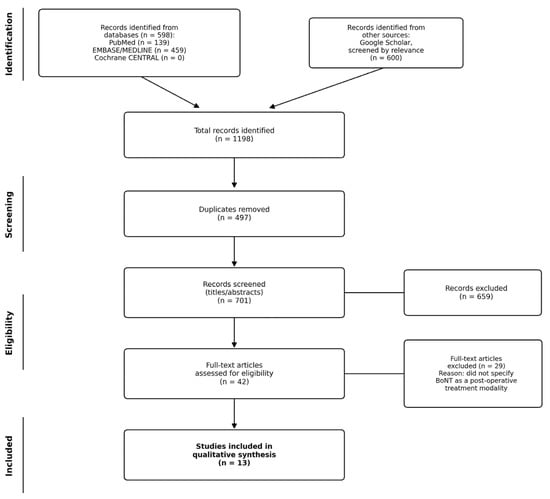
Post-laryngectomy salivary leak and pharyngocutaneous fistula (PCF) are recognised complications that prolong hospitalisation, delay adjuvant treatment and, in severe cases, risk major vessel exposure; current management relies on conservative measures or systemic anticholinergic agents, which carry a substantial burden of unwanted effects. We present four consecutive patients treated with a standardised regimen of botulinum toxin A (BoNT) injected into the parotid tail, parotid body and submandibular gland after failure of conservative management for post-laryngectomy salivary leak/PCF; all four achieved clinical and radiological resolution without significant local or systemic complications. We conducted a narrative review of the literature (PubMed, EMBASE, Cochrane, Google Scholar) using a structured search and screening process, screening 1198 records (701 after deduplication) and identifying 13 eligible studies (231 patients who received BoNT across 12 primary studies) evaluating BoNT for salivary leak/fistula across post-laryngectomy PCF and post-parotidectomy sialocele/fistula populations. A previous systematic review is discussed as supporting context; its patient cohort is not included in the total above, as its 27 source articles may overlap with the primary studies included in this review. Across the case series and a limited, predominantly observational literature base, BoNT was associated with rapid salivary suppression (up to ~95% reduction in one study), high fistula closure rates (54–100%), and accelerated healing, including a statistically significant reduction in healing time in one comparative study (18.5 vs. 26 days, p = 0.008); adverse events were reported as rare and minor, though these findings warrant cautious interpretation given the evidence base. BoNT injection is a low-risk, potentially high-yield adjunct for post-laryngectomy salivary leak and PCF, avoiding the systemic anticholinergic burden of alternative pharmacological treatments; multicentre studies with standardised dosing protocols are needed to establish its role in standard practice.

Flow diagram of the literature search and study selection process (identification, screening, eligibility, and included studies) for this narrative review.
  • Case Report
  • Open Access

Introduction: Acute vertigo presents a diagnostic challenge in the acute stroke setting. Accurate differentiation between a posterior circulation stroke and benign peripheral vestibular disorders is critical for appropriate, timely management. This case highlights the value of a multidisciplinary team approach, including a vestibular physiotherapy assessment and stroke physicians, in a complex acute vertigo presentation. Case Presentation: Mr. G, a 68-year-old male with a past medical history of stroke and hypertension, presented to the Emergency Department with acute-onset vertigo, severe vomiting, and imbalance. He described his symptoms as similar to his previous stroke, raising immediate concern for recurrent cerebrovascular events. Initial CT brain imaging showed no acute pathology. Admission to the hyper-acute stroke unit followed, where standard neurological examination was unremarkable. A HINTS examination and Dix–Hallpike testing performed by the admitting stroke consultant did not yield a definitive diagnosis. Specialist vestibular physiotherapy assessment identified subjective clues and, through systematic positional testing, suggested left apogeotropic horizontal-canal BPPV. The patient was treated successfully with three Gufoni manoeuvres over 24 h. Mr. G was discharged home on a virtual ward, with a subsequent MRI confirming no acute stroke, and telephone follow-up confirming full resolution of symptoms. Conclusions: This case demonstrates the importance of systematic progression through vestibular diagnostic testing and the value of specialist physiotherapy in acute hospital settings. Subjective clues, including positional triggers and symptom exacerbation during CT scanning, contributed decisively to a more likely accurate diagnosis, enabling timely evidence-based treatment and safe, early discharge.

  • Article
  • Open Access

Background/Objectives: To characterize the demographics, inpatient resource utilization, and coded outcomes of pediatric vestibular schwannoma hospitalizations using a national database. Because the Kids’ Inpatient Database records discharges rather than individuals, all measures are reported at the level of the hospital encounter rather than the unique patient. Methods: This was a retrospective cross-sectional study. We analyzed data from the Kids’ Inpatient Database (2003–2019) for patients aged 0–20 years hospitalized with a diagnosis of vestibular schwannoma. Demographics, hospital characteristics, coded adverse diagnoses, surgical intervention, length of stay (LOS), and total charges were assessed. Bivariate and multivariable analyses examined factors associated with surgical resection of vestibular schwannoma. Results: We identified 347 hospitalizations; median age was 16 years and 54.5% were female. Most admissions were for patients who were White (58.5%) and privately insured (68.6%). Surgery occurred in 12.4% of admissions. Surgical stays had longer median LOS (5 vs. 4 days, p = 0.0035) and higher median charges ($82,208.50 vs. $50,723, p = 0.0002). Rates of coded adverse diagnoses during hospitalization were low: facial nerve injury, 12.7%; sensorineural hearing loss, 3.5%; cerebrospinal fluid leak, 0.6%; postoperative infection, 0.9%; and in-hospital mortality, 0.29%. An NF2 diagnosis code was present in 21.9% of hospitalizations, reflecting coded diagnoses rather than true NF2 prevalence, and was more frequent among patients younger than 18 years than among those aged 18–20 years (27.1% vs. 11.9%, p < 0.001). In bivariate comparisons, hydrocephalus (18.6% vs. 8.2%, p = 0.0466) and vagus nerve injury or vocal fold paralysis (9.3% vs. 2.6%, p = 0.0483) were more common among surgical patients. In Firth’s penalized logistic regression, no clinical, demographic, or hospital factor reached significance as an independent predictor of surgery, although the analysis was likely underpowered to detect such associations; trends were observed for vagus nerve injury (OR 4.39, p = 0.065), seizures (OR 2.75, p = 0.077), and vertigo (OR 0.15, p = 0.075). Conclusions: Pediatric vestibular schwannoma hospitalizations are rare, and most admissions did not involve surgical resection during the index hospitalization. When performed, surgery was associated with greater resource use but low rates of coded adverse diagnoses and in-hospital mortality. No factor reached significance as an independent predictor of surgery in the adjusted models, which were likely underpowered given the small number of surgical encounters. Future work linking clinical detail to longitudinal outcomes is needed to refine surgical selection and evaluate potential disparities in care.

  • Article
  • Open Access

Background/Objectives: Artificial intelligence (AI) tools are used in clinical education and patient communication. Concordance with American Academy of Otolaryngology–Head and Neck Surgery Foundation clinical practice guidelines (CPG) and overall readability remain poorly defined. Methods: Over 2 months, ChatGPT, Google Gemini, and Google Search AI were queried using a single LF prompt and a layered set of sub-questions. Responses were scored with a 12-point rubric from the CPG plain-language tonsillectomy guideline. Readability was assessed using Flesch Reading Ease (FRE) and Flesch-Kincaid Grade Level (FKGL). Temporal trends and between-group differences were analyzed using regression and repeated-measures methods. Results: Layered prompts demonstrated greater alignment with guideline subtopics than LF (89.5% vs. 71.4%, p < 0.001). For LF queries, mean concordance was 74.5% (95% CI 72.0–77.0) for Google AI, 71.3% (68.9–73.7) for Gemini, and 68.4% (66.0–70.9) for ChatGPT. Overall, Google AI outperformed Gemini and ChatGPT on pairwise comparisons (p = 0.001). Google AI demonstrated improvement in concordance (slope = 0.03, p = 0.003), while Gemini showed no change (p > 0.05) and ChatGPT worsened over time (slope = −0.03, p < 0.001). Readability differed by strategy and model. Layered prompts produced more accessible text (FKGL 44.6, FRE 10.3) compared with LF outputs (FKGL 35.2, FRE 11.3) and the CPG (FKGL 10.6, FRE 41.7). IRR was high (ICC = 0.96). Conclusions: Model type and prompt structure shaped the quality of AI-generated tonsillectomy guidance. Google AI consistently outperformed ChatGPT, with Gemini intermediate, and uniquely showed temporal improvement. Layered prompting produced more CPG-aligned and readable responses across all models. Readability was consistently above a 7th grade level.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
J. Otorhinolaryngol. Hear. Balanc. Med. - ISSN 2504-463X