


Abstract
Emotional (mental) pain can precipitate a suicidal intention in humans. In contemporary society characterized by an increase in international migrations, the potential impact of immigration remains among the controversial and even quite complex topics in the sociology of suicidal behavior. In other respects, our understanding of the potential impact of immigration status on emotional pain in adults with a dual diagnosis of schizophrenic and comorbid substance use disorders remains unclear. This cross-sectional survey aimed to examine the potential impact of immigration status on the experience of emotional pain. All study participants (N = 93) gave written and signed consent before beginning to complete this individual survey. The analysis revealed significant main effects of both immigration and gender on emotional pain intensity, with the native-born and females reporting a higher intensity of emotional pain. However, no significant effects were found for immigration or gender concerning general self-efficacy. Additionally, significant interactions were found between immigration and gender for both emotional pain intensity and general self-efficacy, with native-born females exhibiting higher emotional pain intensity and general self-efficacy compared to non-native-born females. Regarding the unique contribution of general self-efficacy, the analysis showed that it (but not the lifetime patterns of psychoactive substance use) solely and significantly explained participants’ emotional pain intensity, with higher general self-efficacy associated with lower emotional pain. A mediation analysis revealed that general self-efficacy significantly mediated the relationship between immigration and emotional pain among females, but not males, suggesting that general self-efficacy played a key role in explaining how immigration influenced emotional pain for females with a dual diagnosis of schizophrenic and comorbid substance use disorders. This is the first evidence of the potential impact of immigration status on the experience emotional pain among adults with a dual diagnosis. The general self-efficacy played a key role in explaining how immigration status influenced current emotional pain for females, and not for males, with a dual diagnosis of schizophrenic and comorbid substance use disorders.
1. Introduction
1.1. Suicidal Behavior from the Sociological Aspect
A classical sociological point of view on human suicidal behavior relates to the disconnection process of a person’s ties with society (i.e., anomie suicide) or alternatively an overly integrated society exerting excessive force on people (i.e., altruistic suicide) [1]. Social migration and social norms of psychoactive substance use represent cases of social exclusion of socially vulnerable groups. Not by chance, the social categorization of long distance migration [2,3,4,5] as well as of international immigration [2,4,6,7,8,9,10,11,12,13] and other types of non-native-born populations, such as refugees or asylum/work seekers [14,15], remains among the controversial [16,17] and even quite complex [15] topics in the sociology of suicidal behavior.
Additionally, it has been well established that general self-efficacy varies inversely with the degree of suicidal risk [18]. Otherwise, the sociological research has pointed out that immigrants have lower levels of general self-efficacy than both native-born [19,20,21] and second-generation immigrants [19]. These findings constitute further evidence, albeit indirect, of an increased risk of suicide among immigrants, as opposed to the native-born.
Moreover, about 200,000 Americans die annually from completed suicide or psychoactive substance induced causes. That equates to 550 deaths per day, 22 per hour and one person dying every 3 min. The contemporary world society confronts a new set of social epidemics—psychoactive substance overdoses and suicides. Stated simply, they are signs of serious underlying concerns facing societies worldwide—about suffering, pain and social exclusion [22,23] of socially vulnerable groups.
1.2. Emotional Pain as a Predictor of Suicidal Behavior
According to the suicidologist Edwin Schneidman, suicide is caused by pain; general emotional pain [24]. Orbach and his colleagues [25] defined emotional pain (psychache) as a perception of negative changes in the self that are complimented by negative feelings.
The main insight which emerges from the recent meta-analyses [26,27], systematic [28] and other types of literature review [29,30,31], regarding the hypothetical contribution of emotional pain to suicidal behavior is that emotional pain may precipitate a suicidal intention, i.e., represent a proximal, definitive and direct factor in the initiation of the suicidal behavior.
1.3. The Dual Diagnosis Population as the Socially Vulnerable Group
Dual diagnosis is a broad term used to refer to the presentation of at least one mental illness with at least one psychoactive substance use disorder in the same individual concurrently [32]. The suicide risk in people with dual diagnosis continues to be much higher as compared to the general population [33,34,35,36]. There is consistent and stable data regarding the excess mortality of subjects with severe mental illnesses and lifetime comorbid substance use disorders [34,36,37,38]. Moreover, dually diagnosed individuals, as a socially vulnerable group, have a 2-fold higher suicide risk as compared to those with other categories of mental illness and a 15-fold higher suicide risk as compared to those with psychoactive substance use disorders alone [39].
This study aimed to examine the potential impact of immigration status on emotional pain in socially vulnerable adults with dual diagnosis of schizophrenic and comorbid substance use disorders. The hypotheses in the current study are (1) the intensity of emotional pain and the level of general self-efficacy will differ between males and females and between natives and non-natives; (2) unique contribution of participants’ general self-efficacy will be found in explaining their emotional pain beyond their background characteristics, multiple substance use, route of administration, suicidal tendency, number of hospitalizations, number of days hospitalized, physical comorbidity and other substance use characteristics; (3) due to the lack of research, a question was posed rather than a research hypothesis: does the level of general self-efficacy serve as a mediating variable in the association between gender and emotional pain, and between immigration status and emotional pain?
2. Materials and Methods
2.1. Participants
This study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board of the University Mental Health Facility. Written informed consent was obtained from all subjects involved in the study. The study involved 93 participants with a dual diagnosis of both schizophrenia spectrum and substance use disorders, according to the International classification of diseases and health-related problems—10th edition (ICD-10) [40].
2.2. Measures
2.2.1. Dependent Variable
The Orbach and Mikulincer Emotional Pain Scale (OMMPS) is a self-report, multidimensional instrument designed to assess participants’ current experience of emotional pain intensity [25]. The questionnaire consists of 40 items, each rated on a 5-point Likert scale, ranging from 1 (strongly disagree) to 5 (strongly agree), with higher scores indicating greater emotional pain intensity. The items are divided into 8 dimensions: Irreversibility of Pain, Loss of Control, Narcissistic Wounds, Emotional Flooding, Freezing, Self-Estrangement, Confusion and Emptiness. In the current study, the internal consistency for the total scale, as measured by Cronbach’s alpha, was 0.95. The α reliability for the 9 dimensions was as follows: Irreversibility of Pain (α = 0.77), Loss of Control (α = 0.85), Narcissistic Wounds (α = 0.72), Emotional Flooding (α = 0.74), Freezing (α = 0.66), Self-Estrangement (α = 0.79), Confusion (α = 0.69), Social Distancing (α = 0.39) and Emptiness (α = 0.73).
2.2.2. Independent Variables
The participants were asked various background questions concerning their age, gender, education, marital status, living arrangements and employment. The participants were also asked two additional questions about their history of suicidality: whether they had ever considered suicide and whether they had ever attempted suicide.
The New General Self-Efficacy Scale (NGSES) is an 8-item measure designed to assess general self-efficacy. Items are rated on a 5-point Likert scale, from 1 (strongly disagree) to 5 (strongly agree), with examples such as “I will be able to achieve most of the goals that I have set for myself” and “I am confident that I can perform effectively on different tasks.” Higher scores indicate a higher level of general self-efficacy [41]. In the current study, the internal consistency for the total scale, as measured by Cronbach’s alpha, was 0.70.
Psychoactive substance use measures: the way and frequency of the psychoactive substance use, based on “D” Section “Alcohol/drugs” from Addiction Severity Index—ASI (e.g., “How many days in the past 30 have you used more than one substance per day?”, “How many years in your life have you regularly used more than one substance per day?”) [42].
Charlson Comorbidity Index (CCI) is the most extensively examined physical comorbidity index. The disorders included in this index were selected based on their strength relation to mortality. The index was adapted for use with ICD databases and combined with age to form an age-based comorbidity index [43].
2.3. Statistical Analysis of Data
The sample size was determined a priori by using the G*power software (Version 3.1.9.6). For conducting a two-way MANOVA (Multivariate analysis of variance) analysis, using the test parameters (low effect size = 0.10, α error = 0.05, power = 0.90), the total sample size required was 80 participants.
Prior to addressing the research hypotheses, the skewness and kurtosis values for the measures of emotional pain and general self-efficacy were examined and found to fall within acceptable limits. In addition, before examining the research questions and hypotheses, Pearson correlation analyses were conducted to assess the association between the number of hospitalizations, number of days hospitalized, and lifetime number of substance used, the intensity of emotional pain and the levels of general self-efficacy. These analyses were performed due to significant differences observed between males and females in these variables, as well as between foreign and native-born sub-populations in lifetime substance use. These discrepancies could potentially act as confounding variables.
To test the 1st hypothesis regarding differences in emotional pain and general self-efficacy based on immigration status and gender, a two-way MANOVA was conducted. This analysis was followed by separate two-way ANOVAs for each measure.
To test the 2nd hypothesis, a hierarchical regression analysis was conducted in three blocks. The first block included participants’ background characteristics, multiple substance use, route of administration, suicidal tendency, number of hospitalizations, number of days hospitalized, CCI and other substance use characteristics. The second block included immigration status and gender, the primary independent variables of interest, to assess their unique contribution beyond the effects of the variables entered in the first block. The third block added general self-efficacy to assess its unique contribution to explaining emotional pain.
Lastly, to examine the potential mediating role of general self-efficacy in the association between immigration status and emotional pain, mediation analyses were conducted using Model 4 of the PROCESS software (Version 4.3).
3. Results
3.1. Description of Study Participants
The participants were divided into two populations. The first one consisted of 47 native-born (24 males and 23 females), while the second population comprised 46 immigrants (24 males and 22 females). Table 1 displays the participants’ characteristics by immigration status.
Table 1.
Participant’s characteristics by immigration status (N = 93).
As shown in Table 1, there were no significant differences between the two groups in terms of gender, marital status, and living arrangements [χ2(1) = 0.01, p = 0.915; χ2(1) = 0.12, p = 0.733; χ2(1) = 3.41, p = 0.065, respectively]. A Mann–Whitney test also indicated that the two groups did not differ significantly in terms of educational level and employment status (U = 918.50, p = 0.194 and U = 1020.00, p = 0.615). T-test for two independent samples indicated no significant differences between the two groups in age (t(91) = 0.94, p = 0.348).
Table 2 displays the participants’ multiple substance use, route of administration and suicidal tendency by immigration status.
Table 2.
Participant’s multiple substance use, route of administration and suicidal tendency by immigration status (N = 93).
As shown in Table 2, Chi-square analyses indicated that there were no significant differences between foreign and native-born sub-populations regarding multiple substance use and suicidal thoughts and attempts [χ2(1) = 3.17, p = 0.075; χ2(1) = 0.86, p = 0.353; χ2(1) = 1.10, p = 0.294, respectively]. A Mann–Whitney test also indicated that the two groups did not differ significantly in terms of the most severe route of substance’ administration (U = 996.00, p = 0.438).
Table 3 presents the means, standard deviations (SD) and F-values from the two-way ANOVA (Analysis of variance) for the number of hospitalizations, the number of days hospitalized, CCI and the participant’s characteristics of substance use, comparing these measures by immigration status and gender.
Table 3.
Mean, SD and F values of the number of hospitalizations, number of days hospitalized, CCI and characteristics of substance use by immigration and gender.
As shown in Table 3, a significant main effect of gender was found for number of hospitalizations, number of days hospitalized and lifetime number of substances used. Specifically, males had a significantly higher number of hospitalizations (M = 18.31, SD = 18.35) compared to females (M = 9.96, SD = 10.19) [F(1,89) = 7.43, p = 0.008, ηp2 = 0.08]. Similarly, males were hospitalized for significantly more days (M = 918.35, SD = 907.19) than females (M = 345.24, SD = 484.02) [F(1,89) = 14.27, p < 0.001, ηp2 = 0.14]. In addition, males used a higher number of substances during their lifetime (M = 3.71, SD = 1.44) than females (M = 3.13, SD = 1.22) [F(1,89) = 4.71, p = 0.033, ηp2 = 0.05]. With regard to the lifetime number of substance used, a main effect of immigration status was also found [F(1,89) = 8.20, p = 0.005, ηp2 = 0.08], indicating that native-born participants used a higher number of substances during their lifetime (M = 3.81, SD = 1.38) than foreign-born participants (M = 3.04, SD = 1.25). No interaction effects were found between immigration status and gender concerning the number of hospitalizations, the number of days hospitalized, CCI and substance use characteristics.
Prior to addressing the research hypotheses, the skewness and kurtosis values for the measures of emotional pain and general self-efficacy were examined and found to fall within acceptable limits (skewness between −0.55 and 0.67, and kurtosis between −1.07 and 0.33), indicating that the distributions did not substantially deviate from normality. According to Byrne [44], data is considered normal if skewness falls between −2 and +2, and kurtosis is between −2 and +2.
In addition, before examining the research questions and hypotheses, Pearson correlation analyses were conducted to assess the association between the number of hospitalizations, number of days hospitalized and lifetime number of substances used, the intensity of emotional pain and the levels of general self-efficacy. These analyses were performed due to significant differences observed between males and females in these variables, as well as between foreign and native-born sub-populations in lifetime substance use. These discrepancies could potentially act as confounding variables. Pearson correlation coefficients between the number of hospitalizations, number of days hospitalized and lifetime number of substances used, and the intensity of emotional pain and the levels of general self-efficacy are presented in Table 4.
Table 4.
Pearson correlation coefficients between the number of hospitalizations, number of days hospitalized and lifetime number of substances used, the levels of emotional pain and the intensity of general self-efficacy (N = 93).
As shown in Table 4, no significant correlations were found between participants’ number of hospitalizations, number of days hospitalized or lifetime number of substances used and their intensity of emotional pain or levels of general self-efficacy. This indicates that variations in these characteristics are not statistically associated with either the degree of emotional pain or perceived self-efficacy among the participants. Since no significant associations were found, none of these variables were included as covariates in the subsequent analyses.
3.2. Differences in Emotional Pain and General Self-Efficacy According to Immigration Status and Gender
The first hypothesis proposed that the intensity of emotional pain and the levels of general self-efficacy would differ according to immigration status and gender. To test this hypothesis, a two-way MANOVA was conducted, followed by separate two-way ANOVAs for each measure. The independent variables were immigration status and gender, while the dependent variables were emotional pain and general self-efficacy scores. The mean, standard deviation (SD) and F-values for participants’ emotional pain and general self-efficacy by immigration status and gender are presented in Table 5.
Table 5.
Mean, SD and F-values of the participants’ emotional pain and self-efficacy by immigration status and gender (N = 93).
The MANOVA results revealed significant main effects of immigration status and gender [F(9,81) = 2.91, p = 0.005, ηp2 = 0.24 and F(9,81) = 5.22, p < 0.001, ηp2 = 0.37, respectively]. The interaction between immigration status and gender was marginally significant [F(9,81) = 1.94, p = 0.058, ηp2 = 0.18]. Separate ANOVAs indicated significant main effects of immigration status on the total score for emotional pain and three dimensions of the scale: Loss of Control, Emotional Flooding and Emptiness. Native-born participants scored higher on these measures than foreign-born sub-population. However, contrary to the first hypothesis, no significant main effect of immigration status was found for general self-efficacy.
Additionally, separate ANOVAs revealed a significant main effect of gender for the total score and eight subscales of emotional pain. Females scored significantly higher on these measures than males. However, contrary to the hypothesis, no significant main effect of gender was found for general self-efficacy.
Regarding the interaction between immigration status and gender, separate ANOVAs revealed a significant interaction effect for the total score of emotional pain and four dimensions: Irreversibility, Loss of Control, Narcissistic Wounds and Emptiness. To examine the source of the interaction, simple effects of immigration status were assessed using t-test for the total score and the four dimensions. Results indicated that no significant differences were found between foreign and native-born sub-populations for the total score of emotional pain and the four dimensions among males (p-values ranged from 0.333 to 0.975). However, significant differences were found among females (p-values ranged from 0.003 to <0.001). Specifically, scores on these measures were higher among females who were native-born compared to foreign-born.
Finally, a significant interaction between immigration status and gender was found for general self-efficacy. To examine the source of this interaction, the simple effect of immigration status was assessed using t-test for the general self-efficacy scale. In line with the findings for emotional pain, no significant difference was found between native-born males and foreign-born males in terms of general self-efficacy (p = 0.831). However, a significant difference was observed among females (p = 0.003), with general self-efficacy being lower among native-born females compared to foreign-born females.
3.3. The Unique Contribution of General Self-Efficacy in Explaining Emotional Pain
The second hypothesis of the study proposed that general self-efficacy would make a unique contribution to explaining participants’ emotional pain. To test this hypothesis, hierarchical regression analysis was conducted in three blocks. Block 1 included participants’ background characteristics, multiple substance use, route of administration, suicidal tendency, number of hospitalizations, number of days hospitalized, CCI and other substance use characteristics. These variables were entered using a stepwise approach, meaning that only variables that significantly contributed to explaining emotional pain were included in Block 1. Block 2 added immigration status and gender, with these variables entered in the second block to assess their contribution beyond the variables included in the first block. Block 3 incorporated participants’ general self-efficacy (see Table 6).
Table 6.
Results of the hierarchical regression analysis for participants’ emotional pain (N = 93).
As shown in Table 6, the presence of suicidal thoughts explained 4.9% of the variance in participants’ emotional pain (p < 0.05), with participants who reported suicidal thoughts indicating higher intensity of emotional pain. The participants’ immigration status and gender uniquely contributed 24.1% (p < 0.001) to explaining the intensity of emotional pain, with negative β coefficients suggesting that female participants and native-born tended to report higher intensity of emotional pain. Finally, in line with the second hypothesis, a significant unique contribution of 4.4% (p < 0.05) was found for general self-efficacy, beyond the explanatory variables in the first two blocks. The negative β coefficient indicates that as participants’ general self-efficacy levels increased, their emotional pain intensity decreased.
3.4. The Role of General Self-Efficacy as a Mediating Variable
Given the limited research on this topic, the current study posed a question rather than a formal hypothesis: does the level of general self-efficacy serve as a mediating variable in the association between immigration status and emotional pain among males and females? To examine this question, mediation analyses using Model 4 of the PROCESS software were conducted to assess whether participants’ general self-efficacy mediated the association between immigration status and emotional pain.
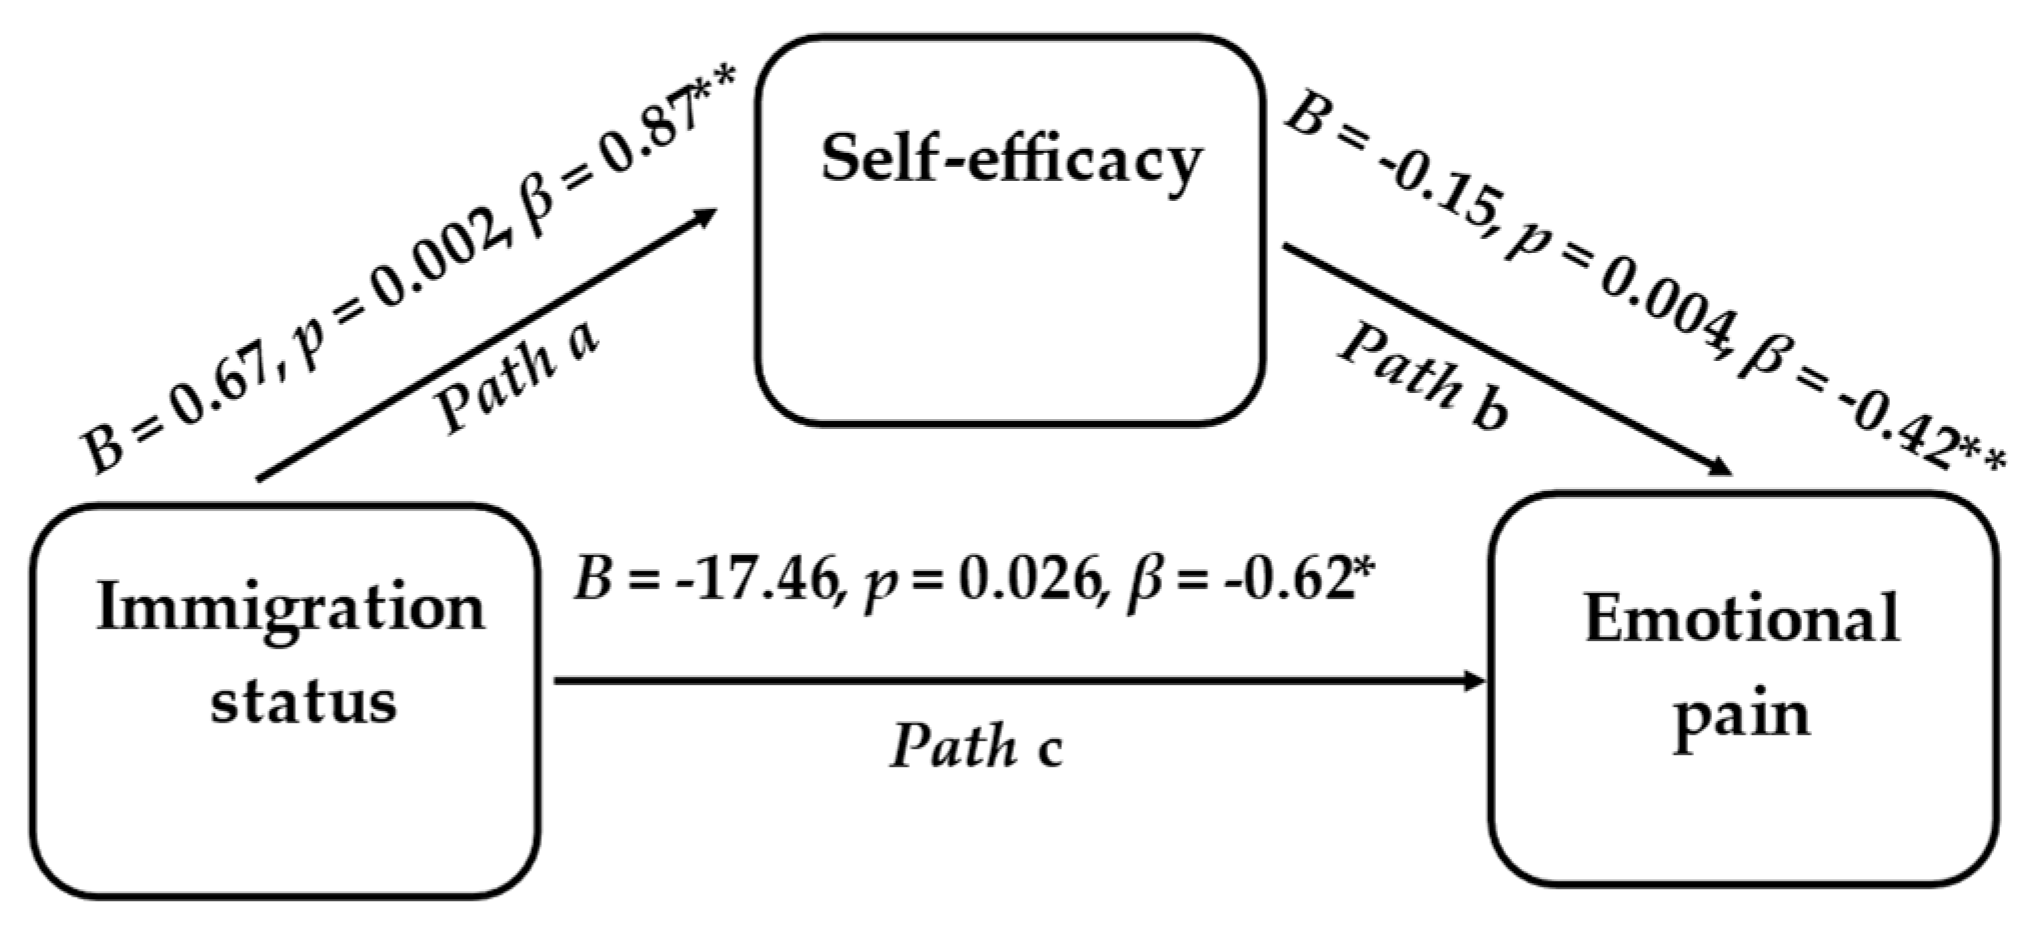
The results among females indicated that the association between immigration status and general self-efficacy (path a) was statistically significant (B = 0.67, SE = 0.21, β = 0.87, p = 0.002, 95% CI = [0.25, 1.10]). The association between general self-efficacy and emotional pain (path b) was significant, (B = −0.15, SE = 4.93, β = −0.42, p = 0.004, 95% CI = [−25.17, −5.25]). The association between immigration status and emotional pain (path c’) was also significant in this mediation model (B = −17.46, SE = 7.56, β = −0.62, p = 0.026, 95% CI [−32.71, −2.22]). The indirect association between immigration status and emotional pain through general self-efficacy among females was statistically significant, as indicated by a bootstrap CI that did not include zero (B = −10.25, BootSE = 5.09, 95% CI [−20.78, −1.27]). The partially standardized indirect association was 0.36 (95% CI [−0.74, −0.05]).
The results among males indicated that the association between immigration status and general self-efficacy (path a) was not statistically significant (B = −0.05, SE = 0.25, β = −0.06, p = 0.831, 95% CI = [−0.56, 0.45]). The association between general self-efficacy and emotional pain (path b) was not significant, (B = −3.22, SE = 5.21, β = −0.09, p = 0.539, 95% CI = [−13.71, 7.27]). The association between immigration status and emotional pain (path c’) was also not significant in this mediation model (B = −2.05, SE = 8.81, β = −0.07, p = 0.817, 95% CI [−19.79, 15.70]). The indirect association between immigration status and emotional pain through general self-efficacy among males was not statistically significant, as indicated by a bootstrap CI that included zero (B = 0.17, BootSE = 1.54, 95% CI [−3.12, 3.68]). The partially standardized indirect association was 0.01 (95% CI [−0.10, 0.13]).
These results mean that, for females, the level of self-efficacy helped explain how their immigration status influenced their emotional pain intensity. However, for males, general self-efficacy did not significantly mediate the relationship between immigration status and emotional pain, indicating that the immigration status did not significantly impact emotional pain through self-efficacy in males (See Figure 1).
Figure 1.
Mediating role of general self-efficacy in the association between immigration status and emotional pain among females with dual diagnosis (N = 45). * p < 0.05; ** p < 0.01.
Path coefficients represent unstandardized (B) and standardized (β) regression weights. Solid arrows indicate statistically significant associations (p < 0.05). The indirect effect of immigration status on emotional pain through general self-efficacy was significant, as indicated by a bootstrap confidence interval that did not include zero.
Relevance to sociology of health: the model suggests that lower general self-efficacy partially explains elevated emotional pain among immigrant females, indicating that self-efficacy may be a clinically modifiable target for interventions aimed at reducing emotional pain in females with DD.
4. Discussion
This study explored the impact of immigration status on emotional pain in socially vulnerable adults with a dual diagnosis of schizophrenic and comorbid substance use disorders. The analysis revealed significant main effects of both immigration and gender on current emotional pain intensity, with native-born and females reporting higher intensity of current emotional pain. However, no significant effects were found for immigration status or gender concerning general self-efficacy. A closer examination revealed the significant interactions between immigration status and gender for both current emotional pain intensity and general self-efficacy, with native-born females exhibiting higher emotional pain intensity and general self-efficacy compared to foreign-born females.
The main explanation for these findings from a sociology of health perspective in the general population lies on the “healthy immigrant effect”. This hypothesis suggests that immigrants would have a lower suicide risk, because they may represent a relatively healthy community within the population in the country of their origin, relatively healthier behaviors of immigrants prior to migration, and immigrant self-selection whereby the healthiest and wealthiest individuals are the people most likely to migrate [12,15,45,46,47,48,49].
Various contemporary empirical evidence from the recent millennium in the general population is consistent with a “healthy immigrant effect”. As opposed to the native population, in different sub-communities, immigration was associated with lower rates of suicide attempts [50,51] and lower suicide mortality rates [45,48,49,50,52,53].
The fact that the phenomenon studied so far in the general population was suicidal behavior (suicide or suicide attempts) should not be ignored. Contrary, in our study of socially vulnerable adults with dual diagnosis, the output measure was the intensity of emotional pain as an expression of suicidal intent.
Regarding the unique contribution of general self-efficacy, the analysis showed that it (but not the social norms of psychoactive substance use) significantly explained participants’ current emotional pain intensity, with higher level of general self-efficacy associated with lower intensity of current emotional pain.
Among the factors found to be the main predictors of the intensity of current emotional pain in adults with dual diagnosis were lifetime suicidal ideation, gender, immigration and general self-efficacy. The four factors explained about a third of the explained variance in the intensity of current emotional pain. It cannot be ignored that none of the substance use characteristics (examined in the present study) were found to predict emotional pain in the population of subjects with schizophrenia spectrum disorders and psychoactive substance addiction. This implies that social norms of drug use (prolonged, simultaneous, frequent use, etc.), which are accepted and appropriate in the dual diagnosis population, may not contribute to predicting the intensity of emotional pain. Consequently, it may not be of substantial importance to take them into account when assessing the potential risk of suicide in this socially vulnerable population of adults with dual diagnosis.
The findings of previous studies indicate a lower level of self-efficacy in new immigrants, compared to natives [19,20,21] and compared to second-generation immigrants [19]. In the current study, this phenomenon was observed only in women. Moreover, self-efficacy was found to mediate the relationship between immigration and current emotional pain only in women. It follows that in order to reduce the intensity of current emotional pain, especially among immigrant women, and consequently reduce the risk of suicide, it is possible to work on improving self-efficacy.
A mediation analysis revealed that general self-efficacy significantly mediated the association between immigration status and current emotional pain among females, but not males. The findings of previous studies have indicated that emotional pain (as measured by OMMPS) serves a mediator in the relationship between various social factors, such as lifetime losses [54], traumatic background in childhood (emotional, sexual, physical abuse; emotional and physical neglect) experience [55,56], experience in close human relationships [57] and suicidality. To the best of our knowledge, this is the first empirical evidence of the contribution of general self-efficacy and additional sociological characteristics (migration, gender) on emotional pain in a socially unintegrated population at significant risk for suicide.
The current study has several limitations. The main one relates to the fact that within-sample comparison was only dichotomous (immigrants versus native-born) and did not address examining the intensity of emotional pain in smaller sub-populations, such as those from the former Soviet Union, Africa [58], etc. An additional limitation is the inclusion of subjects with schizophrenia spectrum disorders only, without reference to other significant mental illness [36]. On the other hand, the impact of emotional pain in depression has been investigated previously [30]. Another limitation is that actual or future suicidal behavior was not examined through prospective follow-up (committing a future suicide attempt, preparing equipment and the environment in preparation for the suicide attempt) [36], but rather a cross-sectional survey of current behavioral intention.
In conclusion, from the sociology of health perspective, the study results suggest that lower general self-efficacy partially explains elevated emotional pain among immigrant females, indicating that self-efficacy may be a clinically modifiable target for interventions aimed at reducing emotional pain in females with a dual diagnosis of schizophrenic and comorbid substance use disorders. Therefore, the current study adds another layer to the understanding of the emotional pain phenomenon.
To the best of our knowledge, this is the first empirical evidence of the potential impact of immigration status on the experience of emotional pain among socially excluded and restricted adults with a dual diagnosis of schizophrenic and comorbid substance use disorders. Taking into account that most clinical samples for psychological pain research have included inpatient participants [25,26,27,28,29,30,31,56,59], the results of this study have a high likelihood for generalizability on the population with dual diagnosis.
Author Contributions
Conceptualization, Y.G. and D.C.; methodology, Y.G. and D.C.; software, Y.G.; validation, D.C. and Y.G.; formal analysis, Y.G.; investigation, Y.G.; resources, Y.G.; data curation, D.C.; writing—original draft preparation, Y.G.; writing—review and editing, D.C.; visualization, Y.G.; supervision, D.C.; project administration, Y.G. and D.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by Institutional Review Board of the University Mental Health Facility (approval code: 182; approval date: 15 October 2024).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The subjects of this individual survey did not give written consent for their data to be shared publicly, so due to privacy and ethical restrictions, as well as due to the highly sensitive nature of the study supporting data is not available.
Acknowledgments
The authors would like to thank the staff at the participating University Mental Health Facility for their assistance. The authors would like to forward special thanks to Inga Novikov (RN, MA) for her continued technical support in this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ANOVA | Analysis of variance |
| ASI | Addiction severity index |
| CCI | Charlson comorbidity index |
| CI | Confidence Interval |
| ICD | International classification of diseases |
| NGSES | New general self-efficacy scale |
| MANOVA | Multivariate analysis of variance |
| OMMPS | Orbach and Mikulincer mental pain scale |
| SD | Standard deviation |
References
- Durkheim, E. Suicide: A Study in Sociology; Routledge: London, UK, 2005. [Google Scholar]
- Kushner, H.I. Immigrant suicide in the United States: Toward a psycho-social history. J. Soc. Hist. 1984, 18, 3–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stack, S. The effects of interstate migration on suicide. Int. J. Soc. Psychiatry 1980, 26, 17–26. [Google Scholar] [CrossRef] [Scilit]
- Toffler, A. Future Shock; Bantam Books: New York, NY, USA, 1971. [Google Scholar]
- Oberg, K. Cultural shock: Adjustment to new cultural environments. Pract. Anthropol. 1960, 4, 177–182. [Google Scholar] [CrossRef] [Scilit]
- Schmid, C.F. Suicide in Minneapolis, Minnesota: 1928–32. Am. J. Sociol. 1993, 39, 30–48. [Google Scholar] [CrossRef] [Scilit]
- Trovato, F. Suicide and ethnic factors in Canada. Int. J. Soc. Psychiatry 1986, 32, 55–64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trovato, F.; Jarvis, G.K. Immigrant suicide in Canada: 1971 and 1981. Soc. Forces 1986, 65, 433–457. [Google Scholar] [CrossRef]
- Shai, D.; Rosenwaike, I. Violent deaths among Mexican-, Puerto Rican-and Cuban-born migrants in the United States. Soc. Sci. Med. 1998, 26, 269–276. [Google Scholar] [CrossRef] [Scilit]
- Taylor, R.; Morrell, S.; Slaytor, E.; Ford, P. Suicide in urban New South Wales, Australia 1985–1994: Socio-economic and migrant interactions. Soc. Sci. Med. 1998, 47, 1677–1686. [Google Scholar] [CrossRef] [Scilit]
- Stack, S. Suicide: A 15-year review of the sociological literature part II: Modernization and social integration perspectives. Suicide Life Threat. Behav. 2000, 30, 163–176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wadsworth, T.; Kubrin, C.E. Hispanic suicide in US metropolitan areas: Examining the effects of immigration, assimilation, affluence, and disadvantage. Am. J. Sociol. 2007, 112, 1848–1885. [Google Scholar] [CrossRef] [Scilit]
- Amiri, S. Prevalence of suicide in immigrants/refugees: A systematic review and meta-analysis. Arch. Suicide Res. 2022, 26, 370–405. [Google Scholar] [CrossRef] [Scilit]
- Breed, W. Occupational mobility and suicide among white males. Am. Sociol. Rev. 1963, 28, 179–188. [Google Scholar] [CrossRef] [Scilit]
- Ratkowska, K.A.; De Leo, D. Suicide in immigrants: An overview. Open J. Med. Psychol. 2013, 2, 124–133. [Google Scholar] [CrossRef]
- Forte, A.; Trobia, F.; Gualtieri, F.; Lamis, D.A.; Cardamone, G.; Giallonardo, V.; Fiorillo, A.; Girardi, P.; Pompili, M. Suicide risk among immigrants and ethnic minorities: A literature overview. Int. J. Environ. Res. Public Health 2018, 15, 1438. [Google Scholar] [CrossRef] [Scilit]
- Wray, M.; Colen, C.; Pescosolido, B. The sociology of suicide. Annu. Rev. Sociol. 2011, 37, 505–528. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Xu, G.; Wu, D.; Yan, M.; Yao, M.; Du, W.; Fan, L. General self-efficacy in association with insomnia symptoms and suicidal ideation among Chinese community-based population. Asia Pac. J. Public Health 2024, 36, 43–50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Motti-Stefanidi, F.; Asendorpf, J.B. Adaptation during a great economic recession: A cohort study of Greek and immigrant youth. Child. Dev. 2017, 88, 1139–1155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duh-Leong, C.; Tomopoulos, S.; Nastro, A.; Sharif, I.; Gomez, L.I.; Di Caprio, C.; Nagpal, N.; Fierman, A.H. Duration of US Residence and Resource Needs In Immigrant Families with Young Children. J. Child. Family Stud. 2022, 31, 211–219. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.E.; Jiang, Y.H.; Dee, V. Psychometric properties of general self-efficacy (GSE) scale Korean version for older Korean immigrants with diabetes: A cross-sectional study in the United States. Nurs. Rep. 2023, 13, 844–854. [Google Scholar] [CrossRef] [Scilit]
- Segal, L.M.; De Biasi, A.; Mueller, J.L.; May, K.; Warren, M.; Miller, B.F.; Norris, T.; Olson, G. Pain in the Nation: The Drug, Alcohol and Suicide Crises and the Need for a National Resilience Strategy. 2017. Available online: https://digitalcommons.providence.org/publications/1096/ (accessed on 7 October 2023).
- Warren, M.; Reavis, B. Pain in the Nation: The Epidemics of Alcohol, Drug, and Suicide Deaths. Special Feature: Polysubstance Use and Emerging Drug Overdose Trends. 2024. Available online: https://www.tfah.org/report-details/pain-in-the-nation-2024/ (accessed on 7 October 2023).
- Schneidman, E.S. Perspectives on suicidology: Further reflections on suicide and psychache. Suicide Life Threat. Behav. 1998, 28, 245–250. [Google Scholar] [CrossRef] [Scilit]
- Orbach, I.; Mikulincer, M.; Sirota, P.; Gilboa-Schechtman, E. Mental pain: A multidimensional operationalization and definition. Suicide Life Threat. Behav. 2003, 33, 219–230. [Google Scholar] [CrossRef] [Scilit]
- Ducasse, D.; Holden, R.R.; Boyer, L.; Artero, S.; Calati, R.; Guillaume, S.; Courtet, P.; Olie, E. Psychological pain in suicidality: A meta-analysis. J. Clin. Psychiatry 2017, 79, 44–51. [Google Scholar] [CrossRef] [Scilit]
- Wang, T.; Yang, L.; Yang, L.; Liu, B.P.; Jia, C.X. The relationship between psychological pain and suicidality in patients with major depressive disorder: A meta-analysis. J. Affect. Disord. 2024, 346, 115–121. [Google Scholar] [CrossRef] [Scilit]
- Verrocchio, M.C.; Carrozzino, D.; Marchetti, D.; Andreasson, K.; Fulcheri, M.; Bech, P. Mental pain and suicide: A systematic review of the literature. Front. Psychiatry 2016, 7, 108. [Google Scholar] [CrossRef] [Scilit]
- Baryshnikov, I.; Isometsä, E. Psychological pain and suicidal behavior: A review. Front. Psychiatry 2022, 13, 981353. [Google Scholar] [CrossRef] [Scilit]
- Gimelfarb, Y.; Cojocaru, D. Psychological and social pain in prediction of suicidality as a societal and adult educational challenge. Educ. 21 J. 2024, 28, 314–326. [Google Scholar] [CrossRef] [Scilit]
- Pompili, M. On mental pain and suicide risk in modern psychiatry. Ann. Gen. Psychiatry 2024, 23, 6. [Google Scholar] [CrossRef] [Scilit]
- United Nations Office on Drugs and Crime—UNODC. Comorbidities in Drug Use Disorders: Discussion Paper; United Nations: New York, NY, USA, 2022; Available online: https://www.unodc.org/documents/drug-prevention-and-treatment/UNODC_Comorbidities_in_drug_use_disorders.pdf (accessed on 20 December 2023).
- Popovic, D.; Benabarre, A.; Crespo, J.M.; Goikolea, J.M.; González-Pinto, A.; Gutiérrez-Rojas, L.; Montes, J.M.; Vieta, E. Risk factors for suicide in schizophrenia: Systematic review and clinical recommendations. Acta Psychiatr. Scand. 2014, 130, 418–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, N.; Dua, T. Landscape analysis: Epidemiology & correlates. In World Health Organization Meeting Report on Excess Mortality in Persons with Severe Mental Disorders; (Publication No. WHO/MSD/MER/16.5); WHO Headquarters: Geneva, Switzerland, 2015; pp. 20–63. Available online: http://www.who.int/mental_health/evidence/excess_mortality_meeting_report.pdf (accessed on 1 November 2022).
- Palma-Álvarez, R.F.; Torales, J.; Barrios, I.; Gurrea Salas, D. Suicide behaviors among patients with substance-induced psychosis: A scoping review. J. Dual Diagn. 2025, 21, 366–377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lucca, G. Assessing Mental Pain as a Predictive Factor of Suicide Risk in a Clinical Sample of Patients with Psychiatric Disorders. Ph.D. Thesis, University of Insubria, Varese, Italy, 2024. Available online: https://irinsubria.uninsubria.it/handle/11383/2170414 (accessed on 19 April 2025).
- Gur, S.; Weizman, S.; Stubbs, B.; Matalon, A.; Meyerovitch, J.; Hermesh, H.; Krivoy, A. Mortality, morbidity and medical resources utilization of patients with schizophrenia: A case-control community-based study. Psychiatry Res. 2018, 260, 177–181. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gimelfarb, Y.; Ligay, A.; Ben Tzarfati, M. Impact of hepatitis B (HBV)/C(HCV) virus co-infection on the long-term survival of patients with schizophrenia and co-occurring substance use disorders. Heroin Addict. Relat. Clin. Probl. 2018, 20, 29–35. [Google Scholar]
- Szerman, N.; Lopez-Castroman, J.; Arias, F.; Morant, C.; Babín, F.; Mesías, B.; Basurte, I.; Vega, P.; Baca-García, E. Dual diagnosis and suicide risk in a Spanish outpatient sample. Subst. Use Misuse 2012, 47, 383–389. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. International Classification of Disease, Version 10. 2019. Available online: https://icd.who.int/browse10/2019/en (accessed on 7 October 2023).
- Chen, G.; Gully, S.M.; Eden, D. Validation of a new general self-efficacy scale. Organ. Res. Methods 2001, 4, 62–83. [Google Scholar] [CrossRef] [Scilit]
- McLellan, A.T.; Luborsky, L.; Woody, G.E.; O’Brien, C.P. An improved diagnostic evaluation instrument for substance abuse patients: The Addiction Severity Index. J. Nerv. Ment. Dis. 1980, 168, 26–33. [Google Scholar] [CrossRef] [Scilit]
- Charlson, M.E.; Pompei, P.; Ales, K.L.; MacKenzie, C.R. A new method of classifying prognostic comorbidity in longitudinal studies: Development and validation. J. Chronic Dis. 1987, 40, 373–383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Byrne, B.M. Structural Equation Modeling with AMOS: Basic Concepts, Applications, and Programming, 2nd ed.; Routledge: London, UK, 2010. [Google Scholar]
- Di Thiene, D.; Alexanderson, K.; Tinghög, P.; La Torre, G.; Mittendorfer-Rutz, E. Suicide among first-generation and second-generation immigrants in Sweden: Association with labour market marginalisation and morbidity. J. Epidemiol. Community Health 2015, 69, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hjern, A.; Allebeck, P. Suicide in first-and second-generation immigrants in Sweden A comparative study. Soc. Psychiatry Psychiatr. Epidemiol. 2002, 37, 423–429. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kennedy, S.; McDonald, J.T.; Biddle, N. The Healthy Immigrant Effect and Immigrant Selection: Evidence from Four Countries; SEDAP Research Paper No. 164; McMaster University: Hamilton, ON, Canada, 2006. [Google Scholar]
- Law, C.K.; Kõlves, K.; De Leo, D. Suicide mortality in second-generation migrants, Australia, 2001–2008. Soc. Psychiatry Psychiatr. Epidemiol. 2014, 49, 601–608. [Google Scholar] [CrossRef] [Scilit]
- Termorshuizen, F.; Wierdsma, A.I.; Visser, E.; Drukker, M.; Sytema, S.; Laan, W.; Smeets, H.M.; Selten, J.P. Psychosis and suicide risk by ethnic origin and history of migration in the Netherlands. Schizophr. Res. 2012, 138, 268–273. [Google Scholar] [CrossRef] [Scilit]
- Kwan, Y.K.; Ip, W.C. Suicidality and migration among adolescents in Hong Kong. Death Stud. 2007, 31, 45–66. [Google Scholar] [CrossRef] [Scilit]
- van Bergen, D.D.; Eikelenboom, M.; Smit, J.H.; van de Looij-Jansen, P.M.; Saharso, S. Suicidal behavior and ethnicity of young females in Rotterdam, the Netherlands: Rates and risk factors. Ethn. Health 2010, 15, 515–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenfield, B.; Rousseau, C.; Slatkoff, J.; Lewkowski, M.; Davis, M.; Dube, S.; Lashley, M.E.; Morin, I.; Dray, P.; Harnden, B. Profile of a metropolitan North American immigrant suicidal adolescent population. Can. J. Psychiatry 2006, 51, 155–159. [Google Scholar] [CrossRef] [Scilit]
- Singh, G.K.; Hiatt, R.A. Trends and disparities in socioeconomic and behavioural characteristics, life expectancy, and cause-specific mortality of native-born and foreign-born populations in the United States, 1979–2003. Int. J. Epidemiol. 2006, 35, 903–919. [Google Scholar] [CrossRef] [Scilit]
- Nahaliel, S.; Sommerfeld, E.; Orbach, I.; Weller, A.; Apter, A.; Zalsman, G. Mental pain as a mediator of suicidal tendency: A path analysis. Compr. Psychiatry 2014, 55, 944–951. [Google Scholar] [CrossRef] [Scilit]
- Zarrati, I.; Bermas, H.; Sabet, M. The relationship between childhood trauma and suicide ideation: Mediating role of mental pain. Ann. Mil. Health Sci. Res. 2019, 17, e89266. [Google Scholar] [CrossRef] [Scilit]
- Pompili, M.; Erbuto, D.; Innamorati, M.; Luciano, M.; Sampogna, G.; Abbate-Daga, G.; Barlati, S.; Carmassi, C.; Castellini, G.; De Fazio, P.; et al. The relationship between mental pain, suicide risk, and childhood traumatic experiences: Results from a multicenter study. J. Clin. Psychiatry 2022, 83, 41432. [Google Scholar] [CrossRef] [Scilit]
- Lutzman, M.; Sommerfeld, E. Mental pain as a mediator in the association between avoidant attachment and suicidal ideation among older men. Aging Ment. Health 2024, 28, 1278–1285. [Google Scholar] [CrossRef] [Scilit]
- Shoval, G.; Schoen, G.; Vardi, N.; Zalsman, G. Suicide in Ethiopian immigrants in Israel: A case for study of the genetic-environmental relation in suicide. Arch. Suicide Res. 2007, 11, 247–253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gimelfarb, Y.; Cojocaru, D. Balancing unemployment and psychache: An individual cross-sectional survey in people with multi-comorbidity. Societies 2026, 16, 35. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.