


Abstract
In the last two and a half years, COVID-19 has been one of the most challenging public health issues worldwide. Based on the available evidence, pregnant women do not appear to be more susceptible to infection than the general population but having COVID-19 during pregnancy may increase the risk of major complications for both the mother and the fetus. The aim of this study is to identify the correlation between BMI and nutritional status and the likelihood of contracting COVID-19 infection in pregnancy, its severity, and maternal pregnancy outcomes. We carry out a systematic literature search and a meta-analysis using three databases following the guidelines of the Cochrane Collaboration. We include 45 studies about COVID-19-positive pregnant women. Compared with normal-weight pregnant women with COVID-19, obesity is associated with a more severe infection (OR = 2.32 [1.65–3.25]), increased maternal death (OR = 2.84 [2.01–4.02]), and a higher rate of hospital admission (OR = 2.11 [1.37–3.26]). Obesity may be associated with adverse maternal and pregnancy outcomes by increasing symptom severity and, consequently, hospital and Intensive Care Unit (ICU) admission, and, finally, death rates. For micronutrients, the results are less definite, even if there seems to be a lower level of micronutrients, in particular Vitamin D, in COVID-19-positive pregnant women.
1. Introduction
In the last few years, the disease caused by SARS-CoV-2 (COVID-19) has presented one of the most challenging public health issues worldwide. The first case of COVID-19 infection was reported in Wuhan, Hubei Province, China, in December 2019, and the infectious disease was classified as a global pandemic by the World Health Organization (WHO) in March 2020 [1]. Thereafter, a high number of new cases and deaths due to COVID-19 were rapidly reported worldwide, affecting the general population as well as pregnant women.
According to the most recent Royal College of Obstetricians and Gynecologists (RCOG) Guidelines on COVID-19 infection in pregnancy, updated in January 2022, pregnant women appear as susceptible to contracting the infection as the general population, and most importantly, more than two-thirds of these women have no severe symptoms; when symptomatic, they generally complain of mild fever and cough [2]. However, a recent systematic review showed that COVID-19 infection in pregnancy is significantly associated with an increased incidence of unfavorable outcomes, such as pre-eclampsia, gestational diabetes, stillbirth, preterm birth, and low birthweight [3]. There is growing evidence that the rather small proportion of pregnant women who display fully symptomatic disease may be at a higher risk of severe complications than their non-pregnant counterparts, particularly in the third trimester of pregnancy, although the overall risk of death remains quite low [2].
Indeed, pregnancy involves unique physiological changes that include the partial suppression of the immune system, on the one hand allowing the body to tolerate the antigenically diverse fetus, while on the other increasing sensitivity to infections. It is well known that most immune cells possess receptors for steroid hormones: the progressively increasing estrogen and progesterone secretion of placental origin modulates the immune response, leading to transient immunosuppression. As a consequence, the mother and fetus become more susceptible to all kinds of infections [4]. Even if the placental barrier effectively prevents viruses from reaching the fetus and causing direct damage, the response of the mother’s immune system itself may negatively affect fetal development [5], thereby increasing the risk of adverse events (miscarriage, pre-eclampsia/eclampsia, intrauterine growth restriction, premature delivery, etc.) [6].
The link between nutrition in pregnancy and COVID-19 infection is suggested by the evidence that the immune response is significantly weakened by an inadequate or imbalanced intake of micronutrients, such as oligoelements and vitamins. The lack or shortage of vitamins and minerals throughout pregnancy may increase the risk of contracting a viral infection and worsening its severity, finally resulting in a higher incidence of pregnancy-related complications [7,8]. Further, a typical nutrition-linked disorder, obesity, has been reported to be a major risk factor for severe COVID-19 disease in pregnancy [9].
Moreover, since implantation and during pregnancy, there are changes in the physiological inflammatory reaction with an increase of oxidative stress that normally is well balanced by the action of reacting oxygen species (ROS) [10,11]. It is reasonable to think that the inflammation mechanism involved in COVID-19 infection, which could be responsible for adverse outcomes [12], may play a synergic role with adiposity-related inflammation in impairing the fine balance of pregnancy.
Taken together, these data suggest that normal body weight and adequate nutrition could be effective in empowering the maternal immune system, thus, better protecting women against all infections, including COVID-19.
In this review and meta-analysis, we analyze how women’s nutritional status (pre-pregnancy overweight/obesity and nutritional deficiencies) may influence the likelihood of contracting COVID-19 in pregnancy, disease severity, and maternal and pregnancy outcomes.
2. Methods
The search strategy followed the guidelines of the Cochrane Collaboration and was deliberately broad in order to increase sensitivity and to include all published articles about COVID-19 infection in pregnancy that reported pre-pregnancy body weight, maternal outcome, fetal outcome, or both. Database-specific searches were applied to PubMed, Embase, and Cochrane Central Register of Controlled Trials, analyzing the available literature published between March 2020 and August 2022.
Search terms were used as free terms. Terms referring to pregnancy, COVID-19, Body Mass Index (BMI), and nutrition were combined with ‘OR’; terms referring to all three were combined with ‘AND’. The following search string was used: (pregnancy OR gestation OR preeclampsia OR stillbirth OR gestational) AND (COVID-19 OR SARS-CoV-2) and (nutrient OR nutrition OR iron OR vitamin OR micronutrients OR minerals OR malnutrition OR diet OR oligoelements OR nutritional OR BMI OR overweight OR obesity). An additional manual search was carried out on the references of the reviewed studies to allow us to identify any additional papers that might have been missed in previous searches. No limits were placed on the search, which was performed in duplicate (by working independently and matching the results).
Abstracts and titles were screened in duplicate by two independent researchers who compared and matched their results and then agreed upon the final selection of the articles. Selected articles were divided into two major categories: those reporting COVID-19 incidence and severity in overweight/obese women and those reporting micronutrient circulating levels, micronutrient intake, and COVID-19 disease.
The following data were extracted: (a) baseline data: title, author, journal, year, country, main objective, study period (as stated in the paper), multicenter or single-center, type of study, number of cases, control group; (b) maternal infection in obese women: death, COVID-19 severity (according to the study definition); (c) micronutrients: any kind of micronutrient deficiency in the mother, nutritional supplementation(s); (d) pregnancy, maternal, fetal, and neonatal outcomes: hypertension, pre-eclampsia, proteinuria, gestational age at delivery, birthweight, preterm delivery, malformations, stillbirth, small for gestational age, admission to neonatal Intensive Care Unit (NICU), other neonatal complications (whenever reported), neonatal death.
In our analysis, we included all articles reporting at least one maternal and/or fetal outcome.
Two reviewers assessed the studies’ quality through the Newcastle–Ottawa Scale independently (NOS) [13]. Controversies were resolved by a third reviewer.
We used the threshold for converting the NOS to AHRQ standards (good, fair, and poor).
Every time it was possible, we performed a meta-analysis producing a pooled estimate of the effect size; in the case of studies’ data not being suitable for meta-analysis, results were presented in a narrative fashion.
Meta-analysis was performed using RevMan 5.4 software [14]
Data are shown as Mantel–Haenszel (M-H) odds ratios (95% CIs) in the case of dichotomous outcomes and as inverse variance (IV) standardized mean differences (95% CIs) in the case of continuous outcomes.
We evaluated heterogeneity with the I2 statistic. If the I2 value was 40% or greater [14], we considered heterogeneity to be present, and thus, we used a random-effects model to pool the data. We performed a sensitivity analysis that used a fixed-effects model for outcomes from studies with small numbers of patients (<100 per arm).
We used funnel plots to assess publication bias.
Ethics Approval
Ethics approval was not sought for this systematic review because the data were publicly available.
3. Results
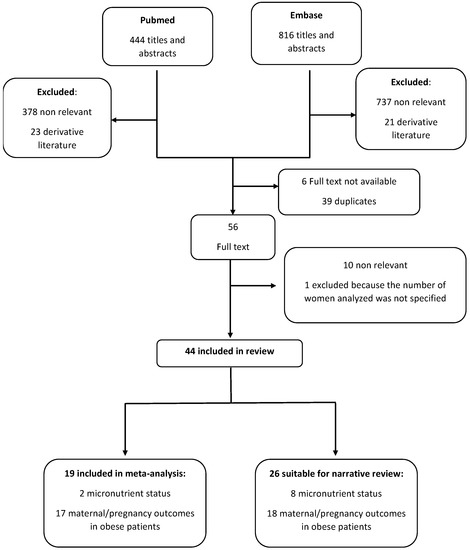
A total of 1260 pertinent titles were retrieved and screened; 56 articles were selected to be considered in full; and 45 more were identified from the reference lists. Finally, the selection process resulted in 35 articles reporting maternal and/or fetal outcomes in overweight/obese women and 10 articles reporting micronutrient deficiency/supplementation in pregnancy (Figure 1). The main characteristics of the studies not suitable for meta-analysis included in the review are reported in Table 1, Table 2, Table 3, Table 4 and Table 5.
Figure 1.
Flow chart for the selection of studies.
The geographic origin of the 35 overweight/obesity studies was the following: 12 from North America, 7 from Central–South America, 13 from Europe, 1 from Asia, 1 from Africa, and 1 was multinational. Six of the ten studies on micronutrients came from Turkey and four from Europe. Most studies were carried out at single centers. The number of women included in the studies regarding overweight/obesity ranged from 5 to 3889, while in studies on micronutrients, it ranged from 15 to 448.
Most studies reported maternal outcomes, while none of the studies analyzed both maternal and fetal outcomes.
3.1. Meta-Analysis
Disease severity (critical/severe vs. mild)
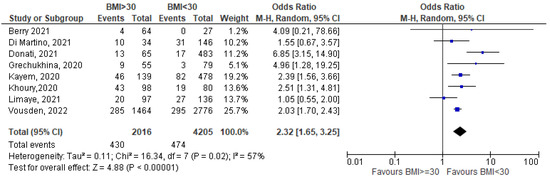
Pooled data show a statistically significant excess of risk of having critical/severe disease for obese (BMI >= 30) pregnant women (OR = 2.32 [1.65–3.25]; I2 = 57%; based on eight studies) [15,16,17,18,19,20,21,22] (Figure 2).
Figure 2.
BMI >= 30 vs. BMI < 30—disease severity (critical/severe vs. mild) [15,16,17,18,19,20,21,22].
Maternal death due to COVID-19-related causes
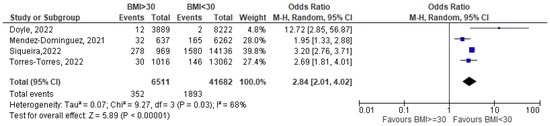
Pooled data show a statistically significant excess of risk of maternal death for obese pregnant women (OR = 2.84 [2.01–4.02]; I2 = 68%; based on four studies) [23,24,25,26] (Figure 3).
Figure 3.
BMI >= 30 vs. BMI < 30—maternal death due to COVID-19-related causes) [23,24,25,26].
Hospital admissions for COVID-19-related causes
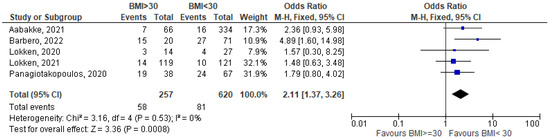
Pooled data show a statistically significant excess of risk of hospital admission for obese pregnant women (OR = 2.11 [1.37–3.26]; I2 =0%; based on five studies) [27,28,29,30,31] (Figure 4).
Figure 4.
BMI >= 30 vs. BMI < 30—hospital admissions for COVID-19-related causes [27,28,29,30,31].
Vitamin D serum levels
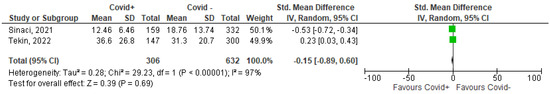
Pooled data show that COVID-19-positive pregnant women have lower vitamin D serum levels when compared with COVID-19-negative pregnant women, but the result is not statistically significant (SMD = −0.15 [−0.89–0.60]; I2 = 97%; based on two studies) [32,33] (Figure 5).
Figure 5.
COVID-19-positive pregnant women vs. COVID-19-negative pregnant women—vitamin D serum levels [32,33].
Sensitivity analysis for all the outcomes goes in the same direction as the main analysis (Appendix A).
The funnel plot for hospital admissions suggests the absence of publication bias (Appendix B).
3.2. Narrative Review
Incidence and severity of COVID-19 infection in overweight/obese pregnant women
Thirty-five articles analyzed the relationship between high BMI (overweight or obesity) and COVID-19 infection incidence and severity. Unfortunately, none of the selected articles were specifically focused on COVID-19 in pregnant women with high BMI; in fact, data on overweight/obese women were extrapolated from large studies on COVID-19 in pregnancy, some of which included obese subjects.
Moreover, the definition of COVID-19 disease severity was highly heterogeneous: some articles simply divided patients into asymptomatic or symptomatic, without specifying the severity of symptoms; in others, the disease was classified as mild, moderate, or critical; and in three articles [25,34,35], the definition of severity was not reported.
Pregnancy outcomes
Only four of the reviewed studies reported pregnancy outcomes.
Three studies reported the pregnancy outcome of obese patients contracting COVID-19 infection during gestation. Vimercati showed that even if BMI was not associated with COVID-19 severity, a higher BMI was significantly associated with preterm birth [36]. Lokken reported the case of one woman with class III obesity (in a cohort of 15 patients), in whom preterm birth was induced to face the progressive worsening of respiratory function [30]. Stenton reported that COVID-19 infection in pregnant obese women was associated with a higher risk of fetal loss vs. pregnant non-obese women (67% vs. 41%) [37].
One study reported pregnancy outcomes in relation to micronutrient deficiency: Citu et al. found a correlation between a lack of magnesium and preterm labor (p = 0.038) [38].
Micronutrient status
We found 10 articles in which micronutrients were considered in relation to COVID-19 disease in pregnant patients. Different aspects were studied: circulating levels of zinc [39,40,41], copper [39,40,41], vitamin D [32,33,40,42], selenium [43], vitamin K1 [41], vitamin E, and Afamin (vitamin E-binding protein) [44]; deficiency of vitamin D [33,40,42,45] or vitamin B12 [40]; and supplementation of vitamin D [40,42] or magnesium [38]. The number of women with COVID-19 infection in each study was relatively small (15–448). The three largest studies analyzed magnesium supplementation (448 women) [38] or vitamin D circulating levels (491 and 347 women) [32,33]. The former reported a significant association between the lack of magnesium and preterm labor (p = 0.038) [38].
Overall, the heterogeneous definitions, design, and results of the published studies precluded the possibility of pooling data and, thus, identifying a clear relationship between micronutrients and the risk of contracting any degree of COVID-19 severity—from mild to severe. The available studies suggest only a slight relationship between low circulating levels of zinc, copper, vitamin B12, vitamin E, and selenium and the likelihood of contracting a severe form of COVID-19 infection.
Table 1.
Association of overweight/obesity with COVID-19 illness severity.
Table 2.
Related maternal mortality.
Table 3.
Association of overweight/obesity with COVID-19 related hospitalization and Internsive Care Unit (ICU) admission.
Table 4.
Association of overweight/obesity with pregnancy outcomes in Covid-19 patients.
Table 5.
Association of micronutrient levels/supplementation with COVID-19 illness severity.
4. Discussion
In 2021, the WHO stated that overweight (BMI > 25 kg/m2) and obesity (BMI > 30 kg/m2) are major risk factors for a relevant number of chronic diseases. These body weight abnormalities affect 40 and 15% of the general population, respectively, with a slightly higher prevalence among women. Nowadays, approximately 28% of pregnant women are overweight, and 11% are obese. Maternal obesity has emerged as a key risk factor for obstetric complications in pregnant women.
Overweight and obesity per se represent well-known risk factors for several adverse obstetric outcomes, both maternal (pre-eclampsia, gestational diabetes, postpartum hemorrhage, etc.) and fetal (preterm birth, large-for-gestational-age infants, intrauterine death, etc.), which together increase maternal, fetal, and neonatal mortality and morbidity. Many health programs aimed at preventing gestational diseases rely on both adequate weight loss and normal body weight in the preconception period, as well as appropriate weight gain during pregnancy.
A higher-than-normal BMI implies a series of complex immunologic, metabolic, and endocrine changes that also affect the immune response to viral infections [9]. It is reasonable to assume that there could be a relationship between overweight/obesity and susceptibility to COVID-19 infection, its severity, and its impact on pregnancy. Indeed, a review of the available literature suggests that there is a positive correlation between overweight/obesity and COVID-19 incidence and severity during pregnancy. Although none of the published studies were specifically designed to detect such an association, it was clearly evident after extrapolating data of pregnant women from large, published databases.
Pregnancy is a key moment for both physical and neurocognitive fetal growth; any nutritional imbalance or deficiency of important nutrients could lead to insufficient and/or impaired fetal development, thus, increasing the risk of unfavorable maternal, fetal, and neonatal outcomes. Micronutrients, such as vitamins A, C, D, and E, and minerals (Fe, Se, and Zn) can actively and effectively boost the immune system, thereby potentially preventing pregnancy complications. In particular, vitamin A is crucial for immune system development. Some authors demonstrated that for a few viral diseases, the supplementation of vitamin A led to a better prognosis and improved outcomes, including clearance of HPV lesions or a reduction in some measles-related complications [60]. Vitamin C protects against infections, vitamin D exerts anti-inflammatory and immunomodulatory effects, and vitamin E is mainly a strong antioxidant and immunomodulatory vitamin that decreases oxidative stress. Serum levels of micronutrients progressively decrease with gestational age due to both physiological hemodilution and increased maternal–fetal demand. Although the available data concerning micronutrients in pregnant women infected with COVID-19 are very heterogeneous and have been obtained in small groups of patients, they suggest the possible existence of a relationship between micronutrient deficiency and the severity of COVID-19 disease, as well a potential role for micronutrient supplementation in preventing and/or attenuating the impact of COVID-19 during pregnancy.
Meta-analysis suggests a net increase in risk (twice or more) for severe disease, maternal death for COVID-19, and hospital admission for COVID-19-related causes for obese pregnant women. Although the results are statistically significant, even if based on a relatively low number of studies, the causal relationship between obesity and adverse outcomes in COVID-19-positive pregnant women must be discussed.
When considering the dose–response criterion, data are in favor of a causal relationship, as with the increase in the obesity class, the risk of adverse events increases too.
There is also a biological plausibility for the association between obesity and adverse COVID-19 outcomes, as we note the same association in different populations, e.g., the general population. In a review on obesity and COVID-19, obesity emerges as one of the major risk factors for COVID-19 severity. According to the review, adiposity-related systemic inflammation, involving cytokine, chemokine, leptin, and growth hormone signaling, and the involvement of hyperactivation of the renin–angiotensin–aldosterone system (RAAS) could play a key role [61].
On the other hand, poor pregnancy outcomes (pre-eclampsia, preterm birth, and stillbirth) are more frequent in COVID-19-positive pregnant women [3]. Furthermore, it is already well known that maternal and pregnancy outcomes are negatively influenced by obesity by increasing maternal and fetal/neonatal morbidity and mortality [62,63,64]. We suppose that obesity could act as a further risk factor in COVID-19-positive pregnancies; unfortunately, we could not perform stratified analysis and meta-regression in order to isolate the impact of obesity, which, in this case, is probably overestimated.
COVID-19 is presently still a worldwide emergency, with thousands of new cases every day, and unfortunately, it may not be the only pandemic we will face, so greater knowledge regarding how to deal with a similar situation could be useful in the future. With these assumptions, we can, therefore, hypothesize the application of a Research Agenda, by creating a list of data to be collected in order to conduct research in which both maternal and fetal outcomes have to be reported, underlying the importance of considering the mother–fetus dyad as a single entity with specific needs.
We suggest that at least the following parameters be considered:
Baseline maternal data: age, ethnicity, BMI, parity, and pre-existing diseases;
Data during pregnancy: gestational age at COVID-19 (or other) infection, symptoms of infection, hospitalization, major complications, maternal death, pre-eclampsia, any other pregnancy complications, and maternal ICU admission;
Delivery data: gestational age at delivery, the reason for induction or for cesarean section, and blood loss at delivery;
Neonatal data: neonatal birthweight, birthweight centile, APGAR score, malformations, stillbirth/neonatal death, admission to neonatal intensive care unit, duration of hospitalization, and other neonatal complications.
Such a common core of data would be useful for carrying out comparisons across settings, as well as for testing new hypotheses and new approaches.
Limitations
We did not register our study with the International Prospective Register of Systematic Reviews (PROSPERO).
As we have highlighted, our study has limitations, some of which are inherent to the original studies. These limitations are likely due to the lack of time during the pandemic and the need to rapidly share experiences. Furthermore, some studies did not involve gynecologists or obstetricians, and thus, pregnancy and fetal outcomes and, as a consequence, pregnancy and/or neonatal complications were underreported.
As the data were observational, we could not control for possible residual confounding.
5. Conclusions
COVID-19 infection can influence the outcome of pregnancy both for the mother and the fetus: its effects may be amplified in women with an impaired nutritional state, including overweight/obesity or by deficiency of macro- and micronutrients.
Further data are needed to better understand how body weight and nutrition can influence the prognosis of COVID-19 in pregnancy, and how pre-pregnancy normalization of BMI and tailored nutritional supplementation can affect pregnancy outcomes [24,26,34,35,36,37,46,47,48,49,50,51,52,53,54,55,56,57,58,59].
Author Contributions
R.A.: designed the study; drafted the study and checked the bibliographic research. M.E.L.: made the bibliographic research; partecipated to the analysis of the data; drafted the study. A.M.: made the bibliographic research and made the tables. E.V.: analysed the data and did the meta-analysis F.P. and A.P.: partecipated to the draft of the study. B.M. and A.R.: drafted the study, overviewed the research. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Figure A1.
(A) Sensitivity analysis including small sample size studies (<100 per arm) and using a fixed effect model. BMI >= 30 vs. BMI <3 0—Disease severity [15,16,17,18,19,20,21,22]. (B) Sensitivity analysis including small sample size studies (<100 per arm) and using a fixed effect model. BMI >= 30 vs. BMI < 30—Hospital admissions [27,28,29,30,31]. (C) Sensitivity analysis including only good quality studies—Disease severity. BMI >= 30 vs. BMI < 30 –. [15,16,17,18,19,20,21,22]. (D) Sensitivity analysis including only good quality studies—Maternal death. [23,24,25,26]. (E) Sensitivity analysis including only good quality studies—Hospital admission. [27,28,29,30,31]. (F) Sensitivity analysis including only good quality studies—Vit D serum levels [32,33].


Appendix B
Figure A2.
(A) Covid+ pregnant women vs. Covid- pregnant women, outcome: 1.1 Vitamin D serum levels. Funnel plot. (B) Funnel plot of comparison: 2 BMI >= 30 vs. BMI < 30, outcome: Disease severity. (C) Funnel plot of comparison: 2 BMI >= 30 vs. BMI < 30, outcome: Maternal death. (D) Funnel plot of comparison: 2 BMI >= 30 vs. BMI < 30, outcome: Hospital admission.


References
- WHO Director-General’s Opening Remarks at the Media Briefing on COVID-19—11 March 2020. Available online: https://www.who.int/director-general/speeches/detail/who-director-general-s-opening-remarks-at-the-media-briefing-on-covid-19---11-march-2020 (accessed on 21 December 2022).
- Coronavirus (COVID-19), Pregnancy and Women’s Health | RCOG. Available online: https://www.rcog.org.uk/guidance/coronavirus-covid-19-pregnancy-and-women-s-health/ (accessed on 21 December 2022).
- Wei, S.Q.; Bilodeau-Bertrand, M.; Liu, S.; Auger, N. The impact of COVID-19 on pregnancy outcomes: A systematic review and meta-analysis. CMAJ 2021, 193, E540–E548. [Google Scholar] [CrossRef] [Scilit]
- Pazos, M.; Sperling, R.S.; Moran, T.M.; Kraus, T.A. The influence of pregnancy on systemic immunity. Immunol. Res. 2012, 54, 254–261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shi, L.; Tu, N.; Patterson, P.H. Maternal influenza infection is likely to alter fetal brain development indirectly: The virus is not detected in the fetus. Int. J. Dev. Neurosci. 2005, 23, 299–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mei, C.; Yang, W.; Wei, X.; Wu, K.; Huang, D. The Unique Microbiome and Innate Immunity During Pregnancy. Front. Immunol. 2019, 10, 2886. [Google Scholar] [CrossRef] [Scilit]
- Wilson, R.L.; Gummow, J.A.; McAninch, D.; Bianco-Miotto, T.; Roberts, C.T. Vitamin and mineral supplementation in pregnancy: Evidence to practice. J. Pharm. Pract. Res. 2018, 48, 186–192. [Google Scholar] [CrossRef] [Scilit]
- Alpert, P.T. The Role of Vitamins and Minerals on the Immune System. Home Health Care Manag. Pract. 2017, 29, 199–202. [Google Scholar] [CrossRef] [Scilit]
- McCartney, S.A.; Kachikis, A.; Huebner, E.M.; Walker, C.L.; Chandrasekaran, S.; Adams Waldorf, K.M. Obesity as a contributor to immunopathology in pregnant and non-pregnant adults with COVID-19. Am. J. Reprod. Immunol. 2020, 84, e13320. [Google Scholar] [CrossRef] [Scilit]
- Kikut, J.; Komorniak, N.; Ziętek, M.; Palma, J.; Szczuko, M. Inflammation with the participation of arachidonic (AA) and linoleic acid (LA) derivatives (HETEs and HODEs) is necessary in the course of a normal reproductive cycle and pregnancy. J. Reprod. Immunol. 2020, 141, 103177. [Google Scholar] [CrossRef] [Scilit]
- Szczuko, M.; Kikut, J.; Komorniak, N.; Bilicki, J.; Celewicz, Z.; Ziętek, M. The role of arachidonic and linoleic acid derivatives in pathological pregnancies and the human reproduction process. Int. J. Mol. Sci. 2020, 21, 9628. [Google Scholar] [CrossRef] [Scilit]
- Tanacan, A.; Oluklu, D.; Koc, B.L.; Sinaci, S.; Beser, D.M.; Hendem, D.U.; Yildirim, M.; Sakcak, B.; Besimoglu, B.; Ersak, D.T.; et al. The utility of systemic immune-inflammation index and systemic immune-response index in the prediction of adverse outcomes in pregnant women with coronavirus disease 2019: Analysis of 2649 cases. J. Obstet. Gynaecol. Res. 2022; Published online. [CrossRef] [Scilit]
- Wells, G.A.; Shea, B.; O’Connell, D.; Peterson, J.; Welch, V.; Losos, M.; Tugwell, P. The Newcastle–Ottawa Scale (NOS) for Assessing the Quality of Nonrandomised Studies in Meta-Analyses. Ottawa: The Ottawa Hospital Research Institute. Available online: www.ohri.ca/programs/clinical_epidemiology/oxford.asp (accessed on 6 February 2023).
- Higgins, J.P.T. (Ed.) Cochrane Handbook for Systematic Reviews of Interventions Version 6.3 (Updated February 2022); Cochrane: 2022. Available online: www.Training.Cochrane.Org/Handbook (accessed on 18 January 2023).
- Berry, M.; Wang, A.; Clark, S.M.; Harirah, H.M.; Jain, S.; Olson, G.L.; Pacheco, L.D.; Saade, G.R.; Saad, A.F. Clinical Stratification of Pregnant COVID-19 Patients based on Severity: A Single Academic Center Experience. Am. J. Perinatol. 2021, 38, 515–522. [Google Scholar] [CrossRef] [Scilit]
- Di Martino, D.; Chiaffarino, F.; Patanè, L.; Prefumo, F.; Vergani, P.; Ornaghi, S.; Savasi, V.; Spinillo, A.; Cromi, A.; D’Ambrosi, F.; et al. Assessing risk factors for severe forms of COVID-19 in a pregnant population: A clinical series from Lombardy, Italy. Int. J. Gynecol. Obstet. 2021, 152, 275–277. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grechukhina, O.; Greenberg, V.; Lundsberg, L.S.; Deshmukh, U.; Cate, J.; Lipkind, H.S.; Campbell, K.H.; Pettker, C.M.; Kohari, K.S.; Reddy, U.M. Coronavirus disease 2019 pregnancy outcomes in a racially and ethnically diverse population. Am. J. Obstet. Gynecol. MFM 2020, 2, 100246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kayem, G.; Lecarpentier, E.; Deruelle, P.; Bretelle, F.; Azria, E.; Blanc, J.; Bohec, C.; Bornes, M.; Ceccaldi, P.-F.; Chalet, Y.; et al. A snapshot of the Covid-19 pandemic among pregnant women in France. J. Gynecol. Obstet Hum. Reprod. 2020, 49, 101826. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khoury, R.M.; Bernstein, P.S.; Debolt, C.; Stone, J.; Sutton, D.M.; Simpson, L.L.; Limaye, M.A.; Roman, A.S.; Fazzari, M.; Penfield, C.A.; et al. Characteristics and outcomes of 241 births to women with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection at Five New York City Medical Centers. Obstet. Gynecol. 2020, 136, 273–282. [Google Scholar] [CrossRef] [Scilit]
- Limaye, M.A.; Roman, A.S.; Trostle, M.E.; Venkatesh, P.; Martinez, M.L.; Brubaker, S.G.; Chervenak, J.; Wei, L.S.; Sahani, P.; Grossman, T.B.; et al. Predictors of severe and critical disease in pregnant women with SARS-CoV-2. J. Matern.-Fetal Neonatal Med. 2021, 35, 7536–7540. [Google Scholar] [CrossRef] [Scilit]
- Vousden, N.; Ramakrishnan, R.; Bunch, K.; Morris, E.; Simpson, N.; Gale, C.; O’Brien, P.; Quigley, M.; Brocklehurst, P.; Kurinczuk, J.J.; et al. Management and implications of severe COVID-19 in pregnancy in the UK: Data from the UK Obstetric Surveillance System national cohort. Acta Obs. Gynecol. Scand. 2022, 101, 461–470. [Google Scholar] [CrossRef] [Scilit]
- Donati, S.; Corsi, E.; Maraschini, A.; Salvatore, M.A.; Baltaro, F.; Boldrini, R.; Bonassisa, S.; Brunelli, R.; Cagnacci, A.; Casucci, P.; et al. The first SARS-CoV-2 wave among pregnant women in Italy: Results from a prospective population-based study. Ann. Ist. Super Sanita. 2021, 57, 272–285. [Google Scholar] [CrossRef] [Scilit]
- Doyle, T.J.; Kiros G egziabhe Schmitt-Matzen, E.N.; Propper, R.; Thompson, A.; Phillips-Bell, G.S. Maternal and perinatal outcomes associated with SARS-CoV-2 infection during pregnancy, Florida, 2020–2021: A retrospective cohort study. Clin. Infect. Dis. 2022, 2 (Suppl. 2), 2020–2021. [Google Scholar] [CrossRef] [Scilit]
- Mendez-Dominguez, N.; Santos-Zaldívar, K.; Gomez-Carro, S.; Datta-Banik, S.; Carrillo, G. Maternal mortality during the COVID-19 pandemic in Mexico: A preliminary analysis during the first year. BMC Public Health 2021, 21, 1297. [Google Scholar] [CrossRef] [Scilit]
- Siqueira, T.S.; de Souza, E.K.G.; Martins-Filho, P.R.; Silva, J.R.S.; Gurgel, R.Q.; Cuevas, L.E.; Santos, V.S. Clinical characteristics and risk factors for maternal deaths due to COVID-19 in Brazil: A nationwide population-based cohort study. J. Travel Med. 2022, 29, taab199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Torres, J.; Martinez-Portilla, R.J.; Espino-Y-Sosa, S.; Estrada-Gutierrez, G.; Solis-Paredes, J.M.; Villafan-Bernal, J.R.; Medina-Jimenez, V.; Rodriguez-Morales, A.J.; Rojas-Zepeda, L.; Poon, L.C. Comorbidity, poverty and social vulnerability as risk factors for mortality in pregnant women with confirmed SARS-CoV-2 infection: Analysis of 13,062 positive pregnancies including 176 maternal deaths in Mexico. Ultrasound Obstet. Gynecol. 2022, 59, 76–82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aabakke, A.J.M.; Krebs, L.; Petersen, T.G.; Kjeldsen, F.S.; Corn, G.; Wøjdemann, K.; Ibsen, M.H.; Jonsdottir, F.; Rønneberg, E.; Andersen, C.S.; et al. SARS-CoV-2 infection in pregnancy in Denmark—Characteristics and outcomes after confirmed infection in pregnancy: A nationwide, prospective, population-based cohort study. Acta Obstet. Gynecol. Scand. 2021, 100, 2097–2110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barbero, P.; Mugüerza, L.; Herraiz, I.; Burguillo, A.G.; Juan, R.S.; Forcén, L.; Mejía, I.; Batllori, E.; Montañez, M.D.; Vallejo, P.; et al. SARS-CoV-2 in pregnancy: Characteristics and outcomes of hospitalized and non-hospitalized women due to COVID-19. J. Matern.-Fetal Neonatal Med. 2020, 35, 2648–2654. [Google Scholar] [CrossRef] [Scilit]
- Lokken, E.M.; Walker, C.L.; Delaney, S.; Kachikis, A.; Kretzer, N.M.; Erickson, A.; Resnick, R.; Vanderhoeven, J.; Hwang, J.K.; Barnhart, N.; et al. Clinical characteristics of 46 pregnant women with a severe acute respiratory syndrome coronavirus 2 infection in Washington State. Am. J. Obstet. Gynecol. 2020, 223, e1–e911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lokken, E.M.; Huebner, E.M.; Taylor, G.G.; Hendrickson, S.; Vanderhoeven, J.; Kachikis, A.; Coler, B.; Walker, C.L.; Sheng, J.S.; Al-Haddad, B.J.; et al. Disease severity, pregnancy outcomes, and maternal deaths among pregnant patients with severe acute respiratory syndrome coronavirus 2 infection in Washington State. Am. J. Obstet. Gynecol. 2021, 225, e1–e77. [Google Scholar] [CrossRef] [Scilit]
- Panagiotakopoulos, L.; Myers, T.R.; Gee, J.; Lipkind, H.S.; Kharbanda, E.O.; Ryan, D.S.; Williams, J.T.; Naleway, A.L.; Klein, N.P.; Hambidge, S.J.; et al. SARS-CoV-2 Infection Among Hospitalized Pregnant Women: Reasons for Admission and Pregnancy Characteristics—Eight U.S. Health Care Centers, 1 March–30 May 2020. Morb. Mortal. Wkly. Rep. 2020, 69, 1355–1359. [Google Scholar] [CrossRef]
- Sinaci, S.; Ocal, D.F.; Yetiskin, D.F.Y.; Hendem, D.U.; Buyuk, G.N.; Ayhan, S.G.; Tanacan, A.; Ozgu-Erdinc, A.S.; Tekin, O.M.; Sahin, D. Impact of vitamin D on the course of COVID-19 during pregnancy: A case control study. J. Steroid Biochem. Mol. Biol. 2021, 213, 105964. [Google Scholar] [CrossRef] [Scilit]
- Tekin, A.B.; Yassa, M.; Birol, P.; Unlu, S.N.; Sahin, T.; Buran, A.M.; Ayanoglu, E.; Tug, N. Vitamin D status is not associated with clinical severity of COVID-19 in pregnant women. Eur. J. Nutr. 2022, 61, 1035–1041. [Google Scholar] [CrossRef] [Scilit]
- Takemoto, M.L.; Menezes, M.O.; Andreucci, C.B.; Knobel, R.; Sousa, L.A.; Katz, L.; Fonseca, E.B.; Nakamura-Pereira, M.; Magalhães, C.G.; Diniz, C.S.; et al. Clinical characteristics and risk factors for mortality in obstetric patients with severe COVID-19 in Brazil: A surveillance database analysis. BJOG 2020, 127, 1618–1626. [Google Scholar] [CrossRef] [Scilit]
- Leal, L.F.; Merckx, J.; Fell, D.B.; Kuchenbecker, R.; Miranda, A.E.; de Oliveira, W.K.; Platt, R.W.; Antunes, L.; Silveira, M.F.; Barbieri, N.B. Characteristics and outcomes of pregnant women with SARS-CoV-2 infection and other severe acute respiratory infections (SARI) in Brazil from January to November 2020. Braz. J. Infect. Dis. 2021, 25, 101620. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vimercati, A.; De Nola, R.; Trerotoli, P.; Metta, M.E.; Cazzato, G.; Resta, L.; Malvasi, A.; Lepera, A.; Ricci, I.; Capozza, M.; et al. COVID-19 Infection in Pregnancy: Obstetrical Risk Factors and Neonatal Outcomes—A Monocentric, Single-Cohort Study. Vaccines 2022, 10, 166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stenton, S.; McPartland, J.; Shukla, R.; Turner, K.; Marton, T.; Hargitai, B.; Bamber, A.; Pryce, J.; Peres, C.L.; Burguess, N.; et al. SARS-COV2 placentitis and pregnancy outcome: A multicentre experience during the Alpha and early Delta waves of coronavirus pandemic in England. EClinicalMedicine 2022, 47, 101389. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Citu, I.M.; Citu, C.; Margan, M.-M.; Craina, M.; Neamtu, R.; Gorun, O.M.; Burlea, B.; Bratosin, F.; Rosca, O.; Grigoras, M.L.; et al. Calcium, Magnesium, and Zinc Supplementation during Pregnancy: The Additive Value of Micronutrients on Maternal Immune Response after SARS-CoV-2 Infection. Nutrients 2022, 14, 1445. [Google Scholar] [CrossRef] [Scilit]
- Anuk, A.T.; Polat, N.; Akdas, S.; Erol, S.A.; Tanacan, A.; Biriken, D.; Keskin, H.L.; Tekin, O.M.; Yazihan, N.; Sahin, D. The Relation Between Trace Element Status (Zinc, Copper, Magnesium) and Clinical Outcomes in COVID-19 Infection During Pregnancy. Biol. Trace Elem. Res. 2021, 199, 3608–3617. [Google Scholar] [CrossRef] [Scilit]
- Yalcin Bahat, P.; Aldikactioglu Talmac, M.; Bestel, A.; Topbas Selcuki, N.F.; Aydın, Z.; Polat, İ. Micronutrients in COVID-19 Positive Pregnancies. Cureus 2020, 12, 10–14. [Google Scholar] [CrossRef] [Scilit]
- Sobczyk, M.K.; Gaunt, T.R. The Effect of Circulating Zinc, Selenium, Copper and Vitamin K1 on COVID-19 Outcomes: A Mendelian Randomization Study. Nutrients 2022, 14, 233. [Google Scholar] [CrossRef] [Scilit]
- Ferrer-Sánchez, N.; Díaz-Goicoechea, M.; Mayoral-Cesar, V.; García-Solbas, S.; Nievas-Soriano, B.J.; Parrón-Carreño, T.; Fernández-Alonso, A.M. Serum 25(OH) Vitamin D Levels in Pregnant Women with Coronavirus Disease 2019 (COVID-19): A Case-Control Study. Int. J. Environ. Res. Public Health 2022, 19, 3965. [Google Scholar] [CrossRef] [Scilit]
- Erol, S.A.; Polat, N.; Akdas, S.; Ayral, P.A.; Anuk, A.T.; Tokalioglu, E.O.; Ayhan, G.; Kesikli, B.; Ceylan, M.N.; Tanacan, A.; et al. Maternal selenium status plays a crucial role on clinical outcomes of pregnant women with COVID-19 infection. J. Med. Virol. 2021, 93, 5438–5445. [Google Scholar] [CrossRef] [Scilit]
- Erol, S.A.; Tanacan, A.; Anuk, A.T.; Tokalioglu, E.O.; Biriken, D.; Keskin, H.L.; Moraloglu, O.T.; Yazihan, N.; Sahin, D. Evaluation of maternal serum afamin and vitamin E levels in pregnant women with COVID-19 and its association with composite adverse perinatal outcomes. J. Med. Virol. 2021, 93, 2350–2358. [Google Scholar] [CrossRef] [Scilit]
- Schmitt, G.; Labdouni, S.; Soulimani, R.; Delamare, C.; Bouayed, J. Oxidative stress status and vitamin D levels of asymptomatic to mild symptomatic COVID-19 infections during the third trimester of pregnancy: A retrospective study in Metz, France. J. Med. Virol. 2022, 94, 2167–2173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Babic, I.; Alsomali, F.; Aljuhani, S.; Baeissa, S.; Alhabib, I.; AlAhmari, E.; Omer, M.; Alkhalifa, K. COVID-19 Pandemic and Its Impact on Perinatal Outcomes between Symptomatic and Asymptomatic Women. Obstet. Gynecol. Int. 2022, 2022, 1756266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Donati, S.; Corsi, E.; Maraschini, A.; Salvatore, M.A.; Arena, M.G.; Boldrini, R.; Brunelli, R.; Cagnacci, A.; Casucci, P.; Cetin, I.; et al. SARS-CoV-2 infection among hospitalised pregnant women and impact of different viral strains on COVID-19 severity in Italy: A national prospective population-based cohort study. BJOG 2022, 129, 221–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galang, R.R.; Newton, S.M.; Woodworth, K.R.; Griffin, I.; Oduyebo, T.; Sancken, C.L.; Olsen, E.O.; Aveni, K.; Wingate, H.; Shephard, H.; et al. Risk Factors for Illness Severity Among Pregnant Women With Confirmed Severe Acute Respiratory Syndrome Coronavirus 2 Infection-Surveillance for Emerging Threats to Mothers and Babies Network, 22 State, Local, and Territorial Health Departments, 29 March. Clin. Infect. Dis. 2021, 73, S17–S23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eskenazi, B.; Rauch, S.; Iurlaro, E.; Gunier, R.B.; Rego, A.; Gravett, M.G.; Cavoretto, P.I.; Deruelle, P.; García-May, P.K.; Mhatre, M.; et al. Diabetes mellitus, maternal adiposity, and insulin-dependent gestational diabetes are associated with COVID-19 in pregnancy: The INTERCOVID study. Am. J. Obstet. Gynecol. 2022, 227, e1–e74. [Google Scholar] [CrossRef] [Scilit]
- Menezes, M.O.; Takemoto, M.L.S.; Nakamura-Pereira, M.; Katz, L.; Amorim, M.M.R.; Salgado, H.O.; Melo, A.; Diniz, C.S.G.; De Sousa, L.A.; Magalhaes, C.G.; et al. Risk factors for adverse outcomes among pregnant and postpartum women with acute respiratory distress syndrome due to COVID-19 in Brazil. Int. J. Gynecol. Obstet. 2020, 151, 415–423. [Google Scholar] [CrossRef] [Scilit]
- Overtoom, E.M.; Rosman, A.N.; Zwart, J.J.; Vogelvang, T.E.; Schaap, T.P.; Akker, T.V.D.; Bloemenkamp, K.W. SARS-CoV-2 infection in pregnancy during the first wave of COVID-19 in the Netherlands: A prospective nationwide population-based cohort study (NethOSS). BJOG 2022, 129, 91–100. [Google Scholar] [CrossRef] [Scilit]
- Péju, E.; Belicard, F.; Silva, S.; Hraiech, S.; Painvin, B.; Kamel, T.; Thille, A.W.; Goury, A.; Grimaldi, D.; Jung, B.; et al. Management and outcomes of pregnant women admitted to intensive care unit for severe pneumonia related to SARS-CoV-2 infection: The multicenter and international COVIDPREG study. Intensiv. Care Med. 2022, 48, 1185–1196. [Google Scholar] [CrossRef] [Scilit]
- Peter, B.; Ree, N.; Ferrer, K.; Younes, L.; Lepe, B.; Manhal, K.; Mydam, J. Risk Factors Associated With COVID-19 Symptoms and Potential Vertical Transmission During Pregnancy: A Retrospective Cohort Study. Cureus 2022, 14, e22900. [Google Scholar] [CrossRef] [Scilit]
- Prasannan, L.; Rochelson, B.; Shan, W.; Nicholson, K.; Solmonovich, R.; Kulkarni, A.; Lewis, D.; Greenberg, M.; Nimaroff, M.; Blitz, M.J. Social determinants of health and coronavirus disease 2019 in pregnancy. Am. J. Obstet. Gynecol. MFM 2021, 3, 100349. [Google Scholar] [CrossRef] [Scilit]
- Sakowicz, A.; Ayala, A.E.; Ukeje, C.C.; Witting, C.S.; William, A.G.; Miller, E.S. Risk factors for severe acute respiratory syndrome. Am. J. Obstet. Gynaecol. MFM 2020, 2, 100198. [Google Scholar] [CrossRef] [Scilit]
- Savasi, V.M.; Parisi, F.; Patanè, L.; Ferrazzi, E.; Frigerio, L.; Pellegrino, A.; Spinillo, A.; Tateo, S.; Ottoboni, M.; Veronese, P.; et al. Clinical findings and disease severity in hospitalized pregnant women with coronavirus disease 2019 (COVID-19). Obstet. Gynecol. 2020, 136, 252–258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Souza, R.T.; Cecatti, J.G.; Pacagnella, R.C.; Ribeiro-Do-Valle, C.C.; Luz, A.G.; Lajos, G.J.; Nobrega, G.M.; Griggio, T.B.; Charles, C.M.; Bento, S.F.; et al. The COVID-19 pandemic in Brazilian pregnant and postpartum women: Results from the REBRACO prospective cohort study. Sci. Rep. 2022, 12, 11758. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vousden, N.; Bunch, K.; Morris, E.; Simpson, N.; Gale, C.; O’Brien, P.; Quigley, M.; Brocklehurst, P.; Kurinczuk, J.J.; Knight, M. The incidence, characteristics and outcomes of pregnant women hospitalized with symptomatic and asymptomatic SARS-CoV-2 infection in the UK from March to September 2020: A national cohort study using the UK Obstetric Surveillance System (UKOSS). PLoS ONE 2021, 16, e0251123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Budhram, S.; Vannevel, V.; Botha, T.; Chauke, L.; Bhoora, S.; Balie, G.M.; Odell, N.; Lombaard, H.; Wise, A.; Georgiou, C.; et al. Maternal characteristics and pregnancy outcomes of hospitalized pregnant women with SARS-CoV-2 infection in South Africa: An International Network of Obstetric Survey Systems-based cohort study. Int. J. Gynecol. Obstet. 2021, 155, 455–465. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinopoli, A.; Caminada, S.; Isonne, C.; Santoro, M.M.; Baccolini, V. What Are the Effects of Vitamin A Oral Supplementation in the Prevention and Management of Viral Infections? A Systematic Review of Randomized Clinical Trials. Nutrients 2022, 14, 4081. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Leeuw, A.J.M.; Luttikhuis, M.A.M.O.; Wellen, A.C.; Müller, C.; Calkhoven, C.F. Obesity and its impact on COVID-19 The obesity pandemic. Published online 2021. [CrossRef]
- Masturzo, B.; Franzè, V.; Germano, C.; Attini, R.; Gennarelli, G.; Lezo, A.; Rolfo, A.; Plazzotta, C.; Brunelli, E.; Youssef, A.; et al. Risk of adverse pregnancy outcomes by pre-pregnancy Body Mass Index among Italian population: A retrospective population-based cohort study on 27,807 deliveries. Arch. Gynecol. Obstet. 2019, 299, 983–991. [Google Scholar] [CrossRef] [Scilit]
- Frey, H.A.; Ashmead, R.; Farmer, A.; Kim, Y.H.; Shellhaas, C.; Oza-Frank, R.; Jackson, R.D.; Costantine, M.M.; Lynch, C.D. Association of Prepregnancy Body Mass Index with Risk of Severe Maternal Morbidity and Mortality among Medicaid Beneficiaries. JAMA Netw. Open 2022, 5, e2218986. [Google Scholar] [CrossRef] [Scilit]
- Saucedo, M.; Esteves-Pereira, A.P.; Pencolé, L.; Rigouzzo, A.; Proust, A.; Bouvier-Colle, M.-H.; Chassard, D.; Cohen, H.; Dreyfus, M.; Ducloy, J.-C.; et al. Understanding maternal mortality in women with obesity and the role of care they receive: A national case-control study. Int. J. Obes. 2021, 45, 258–265. [Google Scholar] [CrossRef] [Scilit]





Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).