Skip to Content
  • 2.2
    Impact Factor
  • 4.1
    CiteScore
  • 28 days
    Submission to First Decision
  • 11 days
    Acceptance to Publication

Livers

Livers is an international, peer-reviewed, open access journal on liver science published bimonthly online by MDPI.
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • High Visibility: indexed within ESCI (Web of Science), Scopus, EBSCO, and other databases.
  • Journal Rank: CiteScore - Q2 (Hepatology)
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 28 days after submission; acceptance to publication is undertaken in 10.9 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (326)

  • Review
  • Open Access

Nuclear receptor coactivator 4 (NCOA4) is the cargo receptor that mediates ferritinophagy, the selective autophagic degradation of ferritin, thereby controlling iron bioavailability. In the liver, this pathway is essential for iron homeostasis, but its dysregulation contributes to ferroptosis and multiple liver diseases. This review aims to summarize the context-dependent roles of NCOA4-mediated ferritinophagy across the pathophysiological spectrum of liver diseases, including drug-induced liver injury, metabolic dysfunction-associated steatotic liver disease, alcoholic liver disease, ischemia–reperfusion injury, liver fibrosis, and hepatocellular carcinoma. We discuss how the pathological versus protective outcomes depend on the cellular redox reserve and the distance from the iron toxicity threshold. We also highlight emerging post-translational modifications that regulate NCOA4 stability and activity, and outline therapeutic strategies for either inhibiting or activating this pathway depending on the disease context. Finally, we discuss priorities for clinical translation, including cell type-specific targeting and biomarker-guided patient stratification.

Livers

9 October 2026
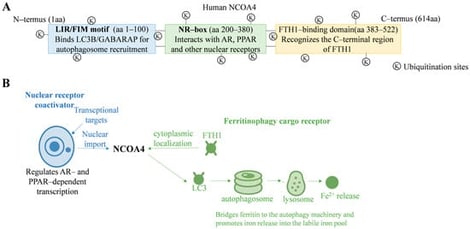
Illustrates the NCOA4 protein’s domain structure, post-translational modifications, and dual functional localization. (A) NCOA4, a 614-amino acid protein, includes: the LIR/FIM motif (aa 1–100) for autophagosomal membrane recruitment via LC3B/GABARAP recognition; the NR box (aa 200–380) for nuclear receptor binding and transcriptional coactivation; and the ferritin-binding domain (aa 383–522) for selective ferritin encapsulation in autophagy. Lysine residues throughout the protein are potential ubiquitination sites affecting its stability. (B) NCOA4 has dual roles in the nucleus and cytoplasm. In the nucleus, it acts as a transcriptional coactivator for nuclear receptors, influencing gene expression like AR and PPAR. In the cytoplasm, NCOA4 serves as a cargo receptor for ferritinophagy, linking FTH1 and LC3 to enable ferritin degradation and release of Fe2+. Its movement between the nucleus and cytoplasm underscores its diverse functions in gene regulation, iron metabolism, and stress responses.
  • Review
  • Open Access

Hepatocellular carcinoma (HCC) is one of the most common malignancies in the world. HCC largely develops in patients with chronic liver diseases, including chronic hepatitis and liver cirrhosis. The surveillance in such patients is extremely important for the detection of HCC as soon as possible. The comprehensive management of HCC is also required because its recurrence frequently occurs. Alpha-fetoprotein (AFP) is widely accepted as a serological tumor marker for HCC and has great diagnostic value. However, its seropositivity is not necessarily suitable for the early detection of HCC. Some novel serological proteins and blood-based biomarkers have been developed in HCC patients who are seronegative for AFP at an early stage. Other serological indicators to predict the recurrence or unfavorable prognosis of HCC have been identified. Moreover, biomarkers to predict treatment outcomes have also been established in those patients. This review summarizes current trends of these serological proteins and blood-based biomarkers for HCC and discusses how to utilize the biomarkers for the early detection and conventional management of HCC.

Livers

2 October 2026

  • Review
  • Open Access

Major Vascular Injury During Laparoscopic Cholecystectomy: The Vasculobiliary Injury Cascade

  • Najoua Rouani,
  • Alessandro Gemini and
  • Nouredin Messaoudi
  • + 4 authors

Laparoscopic cholecystectomy is among the most frequent abdominal operations worldwide, and its safety has improved across three decades. Major vascular injury nonetheless remains a rare but disproportionately lethal complication, capable of producing hepatic ischaemia, biliary stricture, liver failure and death. Bile duct injury has dominated the safety literature; vascular injury—isolated or, more often, combined with bile duct injury as a vasculobiliary injury—has been treated largely as bleeding to be controlled. This review argues that this framing is mistaken. Drawing on the observational literature, guidelines and emerging technologies, it advances one thesis: outcome depends far less on the vessel or repair technique than on where the injury sits on a predictable, systems-level cascade running from distorted anatomy, through cognitive fixation and unsafe dissection, to delayed recognition and non-expert management. We formalise this as the Vasculobiliary Injury Cascade, a three-phase model—predisposition, injury and trajectory—in which every transition is a defensible point of interruption and the determinants of survival lie disproportionately in the final phase. From it we derive a mechanism-specific account of prevention separating arterial misidentification from portal dissection injury, a three-layer defence integrating anatomical recognition, operative decision-making and technology, and a management approach of early recognition and timely referral rather than improvised repair.

Livers

2 October 2026

  • Article
  • Open Access

Background and Objectives: Patients with decompensated cirrhosis often present with multiple concurrent complications, but the prognostic value of the cumulative complication burden remains unclear. This study evaluated the association between the number of concurrent cirrhosis-related complications and 30-day and 60-day mortality and assessed whether complication burden added prognostic information beyond MELD-Na. Materials and Methods: This prospective cohort study included 128 consecutive adults with decompensated cirrhosis admitted to Da Nang Hospital between January and September 2025. Six cirrhosis-related complications were ascertained during the first 48 h of hospitalization: ascites, jaundice, overt hepatic encephalopathy, acute variceal bleeding, spontaneous bacterial peritonitis, and hepatorenal syndrome. Complication burden was defined as the total number of concurrent complications. The primary outcomes were all-cause mortality within 30 and 60 days. Multivariable logistic regression assessed the independent association of complication count with mortality, and predictive performance was compared among MELD-Na, complication count, and their combined model. Results: The median complication count was 2 (interquartile range, 1–3), and 80 patients (62.5%) had at least two complications. Thirty-day and 60-day mortality occurred in 40 (31.3%) and 48 patients (37.5%), respectively. Mortality increased progressively with complication burden. Thirty-day mortality rose from 14.3% among patients with one complication to 23.9%, 54.5%, and 90.0% among those with two, three, and four complications, respectively. Corresponding 60-day mortality rates were 21.4%, 30.4%, 59.1%, and 100.0% (p for trend < 0.001 for both outcomes). Each additional complication was independently associated with increased 30-day mortality (adjusted odds ratio, 2.51; 95% confidence interval, 1.34–4.69) and 60-day mortality (adjusted odds ratio, 2.75; 95% confidence interval, 1.48–5.12). Adding complication count to MELD-Na yielded AUCs of 0.835 and 0.806 for 30-day and 60-day mortality, respectively, with only modest, non-significant improvements in discrimination. Conclusions: Cirrhosis complication burden was independently associated with short-term mortality and provided partly complementary prognostic information beyond MELD-Na, although its incremental predictive value was modest and requires external validation in larger, multicenter cohorts.

Livers

1 October 2026

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

Recent Advances in Acetaminophen Hepatotoxicity
Reprint

Recent Advances in Acetaminophen Hepatotoxicity

Editors: Hartmut W. Jaeschke
Liver Fibrosis
Reprint

Liver Fibrosis

Mechanisms, Targets, Assessment and Treatment
Editors: Ralf Weiskirchen, Tilman Sauerbruch
XFacebookLinkedIn
Livers - ISSN 2673-4389