- Article
15 Pages
Research linking obesity to cellular aging-associated declines in cognitive, physical, and mental health is limited. This cross-sectional study compared relative blood leukocyte telomere length (RTL), cognition (Montreal Cognitive Assessment), fat-free mass, muscle strength, and health-related quality of life between 68 normal-weight and 66 obese Thai women, while exploring the associations between RTL and these outcomes. The results show that the obese group exhibited significantly shorter RTL, alongside lower body mass-normalized fat-free mass and body mass-normalized hand grip strength, higher absolute hand grip strength, and lower scores in specific physical health-related quality of life subdomains compared to the normal-weight group. The adjusted correlation revealed that RTL was positively related to social functioning in the normal-weight group. However, tests for group interaction showed no significant differences in RTL–outcome relationships between groups. Furthermore, there were no longer significant following false discovery rate correction across both groups. These findings suggest that while obesity is associated with shortened cellular aging markers, reduced muscle mass and strength, and diminished physical function, it does not significantly moderate the link between RTL and these health outcomes. Studies with larger sample sizes may be needed to detect potential subtle interaction effects.
Life
8 November 2026
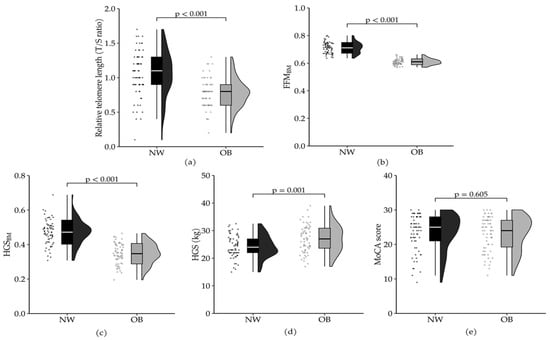
![Raincloud plots comparing RTL (a) FFMBM (b), HGSBM (c), HGS (d), and MoCA score (e) between the NW (n = 68) and OB (n = 66) groups. The Figure displays individual data points [dots with horizontal jitter; black dots (∙) for the NW group and open white dots (∘) for the OB group], kernel density estimates (raincloud distributions), and embedded box plots. Box plots show the median (white horizontal line), interquartile range (IQR; 25th–75th percentiles; box bounds), and whiskers extending to 1.5 × IQR. Normally distributed data are presented as mean ± standard deviation (SD) (b,c), whereas non-normally distributed data are presented as median (IQR) (a,d,e). Between-group differences were tested using the independent t-test for panels (b,c) and the Mann–Whitney U test for panels (a,d,e); p < 0.05 indicates a statistically significant difference. Abbreviation: FFMBM, body mass-normalized fat-free mass; HGSBM, body mass-normalized handgrip strength; HGS, handgrip strength; MoCA, Montreal Cognitive Assessment; NW, normal-weight; OB, obese.](https://mdpi-res.com/life/life-16-01889/article_deploy/html/images/life-16-01889-g001-550.jpg)
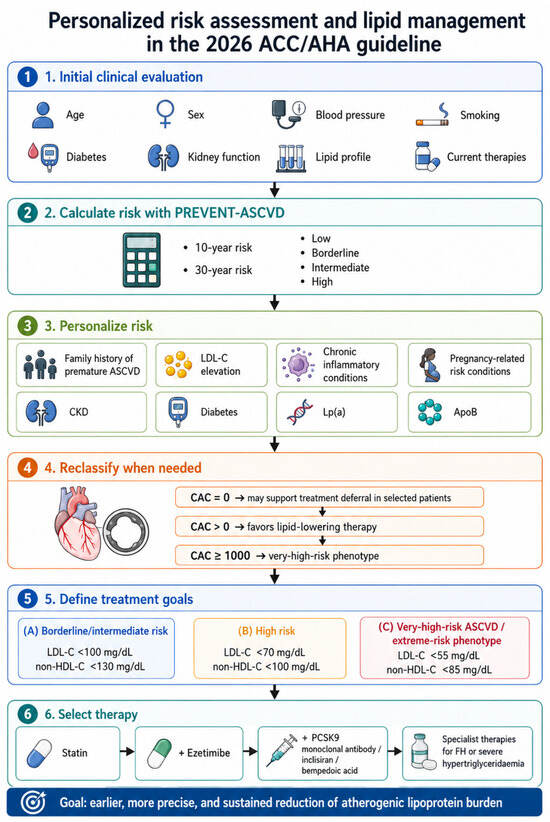
![Personalized risk assessment and lipid management in the 2026 ACC/AHA guideline. The 2026 ACC/AHA framework for dyslipidemia management moves from a single-score approach to a layered strategy integrating initial clinical evaluation, PREVENT-ASCVD risk estimation, risk-enhancing factors, selective use of lipoprotein(a) [Lp(a)] and apolipoprotein B (ApoB), and coronary artery calcium (CAC) for risk reclassification. The resulting risk profile informs the definition of LDL-C and non-HDL-C treatment goals and the selection of lipid-lowering therapy, from statins to combination treatment and specialist therapies in selected phenotypes. Overall, this model supports earlier, more precise, and sustained reduction in atherogenic lipoprotein burden. Abbreviations: ACC, American College of Cardiology; AHA, American Heart Association; ApoB, apolipoprotein B; ASCVD, atherosclerotic cardiovascular disease; CAC, coronary artery calcium; CKD, chronic kidney disease; LDL-C, low-density lipoprotein cholesterol; Lp(a), lipoprotein(a); PREVENT-ASCVD, Predicting Risk of cardiovascular disease EVENTs–Atherosclerotic Cardiovascular Disease.](https://mdpi-res.com/life/life-16-01470/article_deploy/html/images/life-16-01470-g001-550.jpg)