


Highlights
What are the main findings?
- Studies with the lowest risk of bias mostly showed no significant correlations between cerebral oxygenation and acid base status.
What is the implication of the main finding?
- Further well-designed studies with minimal risk of bias are necessary to clarify this issue.
Abstract
Introduction: Blood gas analysis is utilized to assess parameters of oxygenation and ventilation, including acid–base status [pH value, base excess (BE) or base deficit (BD), and bicarbonate (HCO3)], to evaluate systemic metabolism status. Acid–base imbalances can have complex effects on the organism, potentially impacting oxygen delivery to tissue. Cerebral oximetry is a non-invasive monitoring technique using near-infrared spectroscopy (NIRS) for the continuous measurement of cerebral tissue oxygenation. The relationship between the acid–base status and cerebral tissue oxygenation in neonates remains unclear. This systematic qualitative review aims to analyze current knowledge of the potential correlations between different acid–base status parameters and cerebral tissue oxygenation measured via NIRS in neonates. Methods: A systematic search of PubMed and Ovid Embase was performed, focusing on cerebral oxygenation, neonates, and acid–base status. Risk of bias was assessed using the ‘‘Risk of Bias for Non-randomized Studies of Exposures’’ (ROBINS-E) instrument. Results: Fifty studies that measured parameters of the acid–base status and cerebral tissue oxygenation in the neonatal period were identified. Seven studies demonstrated a correlation between pH and cerebral tissue oxygenation, while eleven studies found no such correlation. Five studies demonstrated a correlation between the BE/BD and cerebral tissue oxygenation, while six studies found no such correlation. Three studies demonstrated a correlation between HCO3 and cerebral tissue oxygenation, while five studies found no such correlation. Discussion: Associations between acid–base status parameters and cerebral tissue oxygenation remain controversial. However, studies with the lowest risk of bias mainly demonstrated no significant correlation between any of the acid–base status parameters and cerebral tissue oxygenation.
1. Introduction
Cerebral injuries, such as intraventricular haemorrhage (IVH) or periventricular leukomalacia (PVL), remain persistent challenges in neonatology [1,2,3,4]. The neonatal cerebral autoregulation mechanism plays a crucial role in maintaining stable cerebral perfusion and oxygenation. Impairment of these mechanisms can result in hyperoxic or hypoxic conditions, potentially resulting in irreversible complications, such as IVH or PVL [2,3,5,6,7,8]. IVH and PVL are particularly common in extremely preterm infants, and they are associated with poor neurodevelopmental outcome or death [1,9,10,11]. Understanding the physiology and pathophysiology of neonatal cerebral autoregulation and its influencing factors is essential for the prevention of these irreversible severe complications. A major challenge remains—the timely recognition of impaired neonatal cerebral autoregulation and the subsequent imbalance in cerebral oxygen supply and consumption before cerebral complications occur. Unfortunately, current routine monitoring during the neonatal period, including pulse oximetry, electrocardiogram, and blood pressure measurement, does not assess cerebral oxygen delivery or cerebral oxygen consumption, thereby neglecting potentially critical cerebral oxygenation information [12,13,14,15].
Cerebral oximetry is a continuous, non-invasive, real-time method using near-infrared spectroscopy (NIRS) to detect cerebral tissue oxygenation [cerebral regional oxygen saturation (crSO2), tissue oxygenation index (TOI), and fractional tissue oxygen extraction (FTOE)]. Cerebral tissue oxygenation depends on cerebral oxygen delivery, cerebral oxygen consumption, and the arterial–venous volume ratio [16,17]. Therefore, using NIRS might be a promising tool for detecting impairments in cerebral perfusion and oxygenation even when routine monitoring parameters still remain within normal ranges [15,18,19]. Research has identified various variables, including cardiovascular and respiratory parameters, that may influence cerebral tissue oxygenation in neonates [17,20,21,22].
Blood gas analysis is a quick and non-invasive point-of-care method for assessing the acid–base status, identifying insufficient systemic oxygenation, and guiding counter-regulation in hypoxic conditions. Acid–base status parameters can serve as outcome predictors and indicators for interventions in neonates [23,24,25]. The pH level may affect neonatal vascular tone, subsequently influencing cerebral oxygen delivery and thus cerebral tissue oxygenation [26]. Furthermore, acidosis is associated with an increased risk for cerebral complications, such as hypoxic ischemic encephalopathy (HIE), IVH, or seizures [27,28,29]. Parameters such as base excess (BE) or its reversal, the base deficit (BD), and bicarbonate (HCO3) indicate the counter-regulation of an impaired acid–base status, and deviations are important predictors of neonatal morbidity, such as HIE, seizures, or respiratory complications [27,28,30,31]. Additionally, the administration of HCO3 in neonates with metabolic acidosis is a potential treatment option, although its benefits and harms remain controversially debated [29,32]. There is increasing research interest concerning the impact of acid–base status parameters on cerebral tissue oxygenation in neonates [33,34,35]. However, the effects of acid–base status parameters on the autoregulation mechanism and subsequently on cerebral oxygenation in the neonatal brain are unclear. The aim of this review is to provide an overview of the current literature regarding a potential association between parameters of the acid–base status and cerebral oxygenation in neonates during the neonatal period.
2. Materials and Methods
2.1. Search Strategy and Selection Criteria
Studies were identified using the stepwise approach outlined in the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA 2020) statement [36]. To ensure transparency and reproducibility, we pre-registered our study protocol in the International Prospective Register of Systematic Reviews database (PROSPERO, Registration ID: CRD420250655009).
2.2. Eligibility Criteria
Studies were included if they reported cerebral tissue oxygenation measurements with NIRS (crSO2 or FTOE), along with acid–base status parameters (pH, BE, BD, and HCO3), in neonates during the neonatal period.
2.3. Search Strategy
A systematic search was conducted on PubMed NCBI and Ovid Embase to identify studies published in the English language between July 1977—the first description of NIRS application in neonates—and May 2025. The search keywords included the following: near-infrared spectroscopy, fractional tissue oxygen extraction, regional cerebral tissue oxygen saturation, oxygenation, term neonates, preterm neonates, newborns, baby, caesarean delivery, vaginal delivery, transition, after birth, neonatal transition, metabolism, pH value, bicarbonate, base-excess, base-deficit, acidosis, alkalosis, acid-base balance, and acid-base imbalance.
2.4. Inclusion and Exclusion Criteria—Population
To be eligible, studies had to investigate human neonates with a postnatal age of less than 28 days. Studies that included both neonates with a postnatal age of less than 28 days and older infants or children were also included. Animal studies and studies without an available abstract were excluded.
2.5. Inclusion and Exclusion Criteria—Measurements (Exposure)
Studies using any NIRS device for cerebral oximetry were included if any additional measurements of neonatal capillary, venous, or arterial blood pH, BE/BD, or HCO3 values were reported.
2.6. Inclusion and Exclusion Criteria—Types of Publication
We included all studies published in the English language, excluding non-original articles, such as comments, book chapters, editorials, reviews, and methodological papers. Duplicates and publications in non-English languages were also excluded.
2.7. Study Selection
The articles identified in the literature review were independently evaluated by two authors (C.M. and G.P.) based on the titles and the abstracts. Full texts were then retrieved according to the eligibility criteria. In cases of uncertainty regarding inclusion based on the abstract, the full text was also assessed. Any disagreements were resolved through discussion and consensus between the two authors. Data were qualitatively analysed, including the study design, study population (preterm/term neonates), number of neonates, NIRS device used, NIRS measurement time point and duration, acid–base status parameter measurement time point, values of NIRS parameters and acid–base status parameters, the presence or absence of association, and the direction of correlation if an association was detected.
2.8. Risk of Bias in Individual Studies
During the planning process of this review, we primarily expected non-randomized observational studies. The bias assessment of non-randomized observational studies through standard bias assessment tools, such as the Newcastle–Ottawa Scale, resulted in a lack of feasibility. Hence, the Risk of Bias in Non-randomized Studies of Exposures (ROBINS-E) tool was used for studies presenting data on associations between parameters of the acid–base status and cerebral oxygenation [37]. The assessment process was conducted using the standardized ROBINS-E Excel implementation. ROBINS-E is a tool for assessing the risk of bias in non-randomized studies and includes seven items: (I) risk of bias due to confounding; (II) risk of bias arising from measurement of the exposure; (III) risk of bias in the selection of participants for the study; (IV) risk of bias due to post-exposure interventions; (V) risk of bias due to missing data; (V.) risk of bias arising from measurements of the outcome; and (VII) risk of bias in the selection of the reported result [36]. Each bias item was rated as low, some concerns, high risk, or very high risk of bias. Confounding factors were defined as follows: i. impaired cerebral autoregulation mechanism; ii. disorders of the cardiovascular system; iii. disorders of the respiratory system; iv. disorders resulting in increased oxygen consumption; and v. congenital malformation. Finally, a complete risk-of-bias rating was assigned to each study for the given answer on the observed presence or absence of association. Studies were categorized as low/some concerns (=low) risk of bias and high/very high (=high) risk of bias to address potential confounding.
3. Results
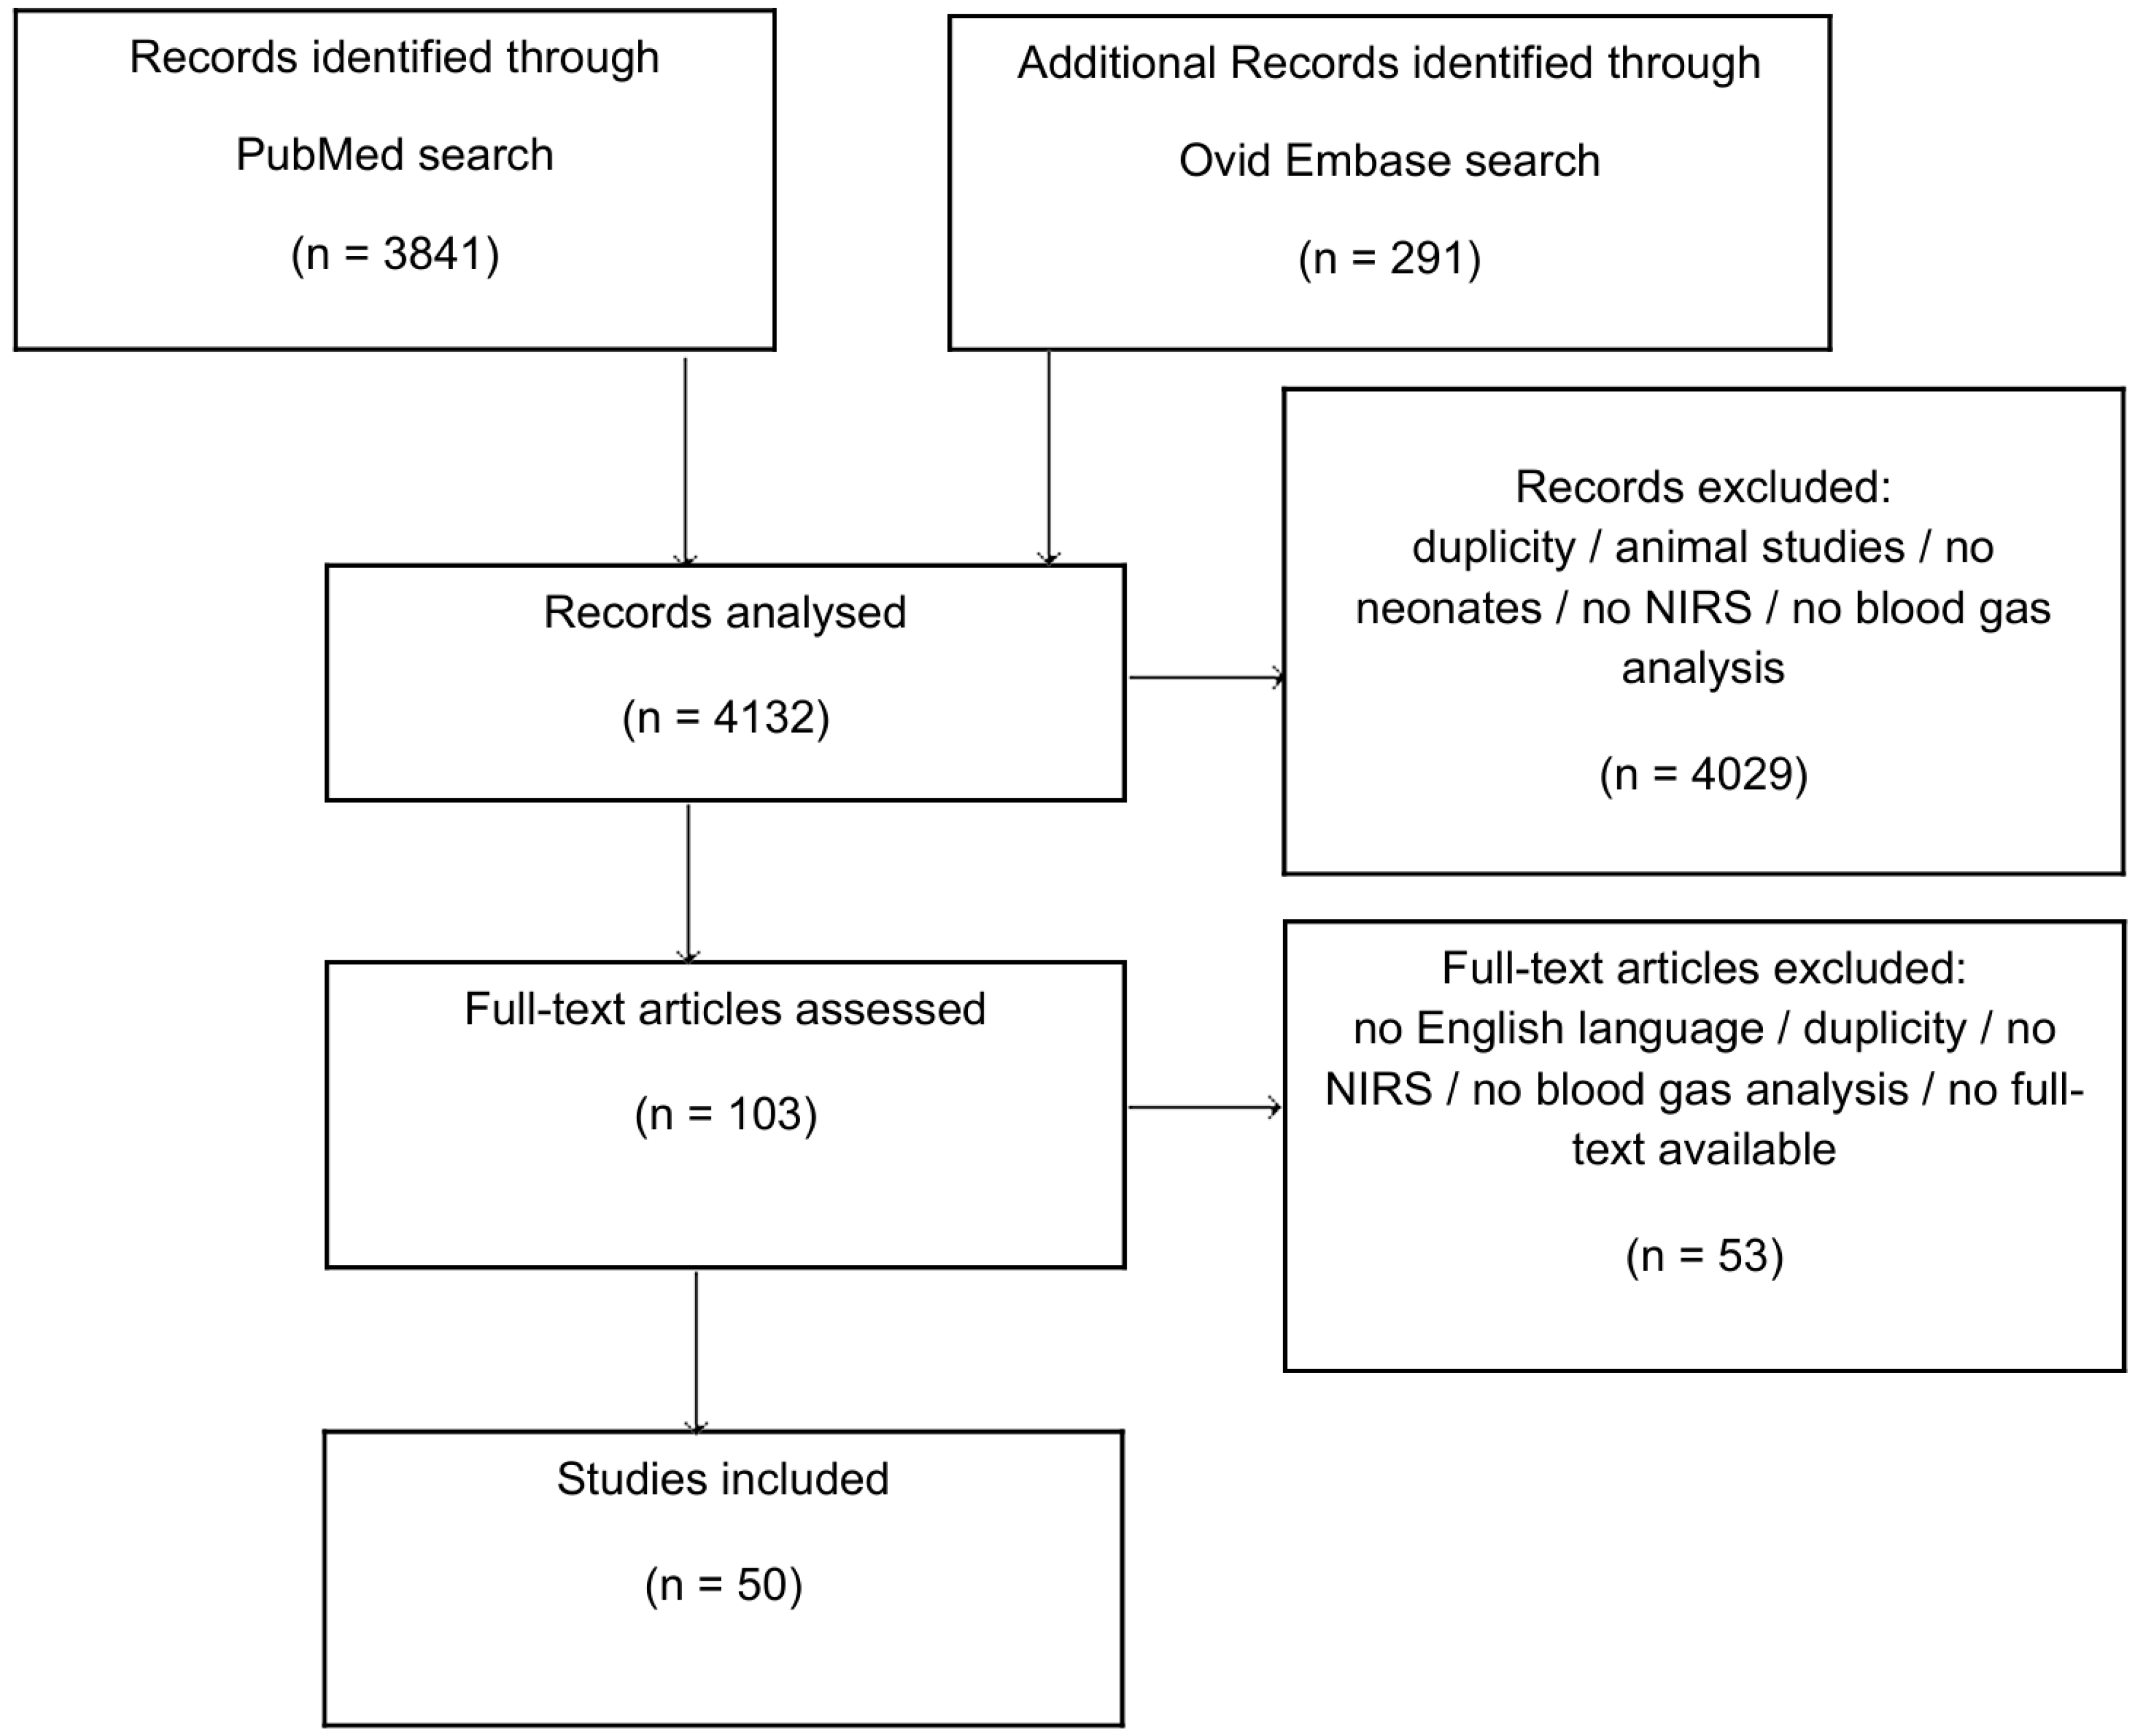
From the preliminary search, 4132 abstracts were identified and assessed for eligibility. Following the full-text review, 50 studies met the inclusion criteria for this systematic review [26,34,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81,82,83,84,85] (Figure 1).
Figure 1.
PRISMA flow chart; NIRS = near-infrared spectroscopy.
In total, 21 studies [38,39,40,41,44,45,48,49,50,52,53,57,60,62,66,67,78,79,80,82,83] analyzed two parameters, and 9 studies [34,46,54,63,68,69,71,72,85] reported on all three parameters of the acid–base status in combination with NIRS measurements during the neonatal period. Table 1, Table 2 and Table 3 provide an overview of the basic data of all included studies.
Table 1.
pH and cerebral oxygenation in the neonatal period.
Table 2.
Base excess/base deficit and cerebral oxygenation in the neonatal period.
Table 3.
Bicarbonate and cerebral oxygenation in the neonatal period.
3.1. pH Value and Cerebral Tissue Oxygenation
A total of 50 studies reported pH and cerebral NIRS measurements [26,34,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81,82,83,84,85] (Table 1).
Seven studies reported an association between the pH and cerebral tissue oxygenation (crSO2 and FTOE). Of these, four studies [34,38,72,83] found a positive correlation, while three studies [26,69,79] found a negative correlation. Eleven studies demonstrated no association [43,44,46,57,63,64,68,74,75,80,85], while thirty-one studies did not find an association [39,40,41,42,45,47,48,49,50,51,52,53,54,55,56,58,59,60,61,62,65,66,67,70,71,73,76,77,78,81,82].
3.2. Base Excess (BE) or Base Deficit (BD) and Cerebral Tissue Oxygenation
A total of 26 studies were identified that reported on BE or BD in combination with cerebral NIRS measurements [34,38,40,41,44,45,46,48,49,50,52,53,54,57,60,62,63,66,68,69,71,72,78,79,83,85] (Table 2).
Five studies found an association between BE and cerebral tissue oxygenation, with four studies [38,69,72,79] reporting a negative correlation and one study [34] reporting a positive correlation. Six studies found no associations [44,46,63,68,83,85], while fifteen studies did not find an association [40,41,45,48,49,50,52,53,54,57,60,62,66,71,78].
3.3. Bicarbonate (HCO3) and Cerebral Tissue Oxygenation
A total of 13 studies were identified that reported on HCO3 measurements in combination with cerebral NIRS measurements [34,39,46,54,63,67,68,69,71,72,80,82,85] (Table 3).
Three studies found an association between HCO3 and cerebral tissue oxygenation. Of these, one study [69] reported a negative correlation, while one study [72] reported a positive correlation. Additionally, one study reported a positive correlation between HCO3 and fractional tissue oxygen extraction (FTOE) only in term neonates but not in preterm neonates [34]. Five studies demonstrated no associations [46,63,68,80,85], while five studies did not find an association [39,54,67,71,82].
3.4. Quality Assessment and Risk of Bias Assessment
Eighteen of these studies provided data on the potential association between acid–base status parameters and cerebral tissue oxygenation [26,34,38,43,44,46,57,63,64,68,69,72,74,75,79,80,83,85]. Quality assessment and risk of bias were assessed for all included studies. Overall, study quality varied (Table 4).
Table 4.
Quality of included studies as assessed using the Risk of Bias in Non-Randomized Studies of Exposure (ROBINS-E) tool.
No studies were categorized as low risk. Five studies (27.7%) were categorized as having some concerns, seven studies (38.8%) as high risk, and five studies (33.3%) as very high risk according to the ROBINS-E tool. Table 4 provides an overview of the risk-of-bias assessment. Most included studies were prospective observational studies (66%), followed by retrospective analyses (16%), randomized controlled trials (10%), cross-sectional studies (2%), and case–control studies (4%). An overview of the ROBINS-E assessment and the correlation between the acid–base status parameters and cerebral tissue oxygenation is presented in Table 5.
Table 5.
Overview of ROBINS-E (risk-of-bias assessment) and correlations between parameters of the acid–base status and cerebral oxygenation in neonates during the neonatal period.
4. Discussion
This systematic qualitative review demonstrates that associations between acid–base status parameters and cerebral tissue oxygenation in neonates are controversial. These conflicting results may arise from different factors, including the diverse populations studied, variations in measurement timing, and differing clinical contexts.
4.1. pH Value and Cerebral Tissue Oxygenation
Low pH values may indicate inadequate oxygen supply and/or impaired gas exchange, potentially resulting in irreversible cerebral injury or death [27,28,29]. Studies have reported both negative and positive correlations between pH and cerebral tissue oxygenation. A negative correlation has been observed in neonates, infants, and young children undergoing pediatric heart surgery [26], in those with infantile hypertrophic pyloric stenosis in the perioperative setting [69], and in healthy full-term neonates during the first 10 min of extrauterine life [79]. Conversely, positive correlations have been reported in fetuses shortly before delivery [38]; in preterm and term neonates during the first 15 min after birth [34]; in extremely preterm neonates on the first day after birth [72]; in term-born asphyxiated neonates immediately before the initiation of therapeutic hypothermia [83]; and in preterm neonates with and term neonates without respiratory support during the first 15 min after birth [85]. These discrepancies may be attributed to variations in sample size, timing, and interval between measurements of acid–base status parameters and cerebral tissue oxygenation, and the clinical setting (e.g., HCO3 administration, surgical procedures).
4.2. Base Excess (BE) or Base Deficit (BD) and Cerebral Tissue Oxygenation
The BE or BD, in combination with the pH, is used alongside clinical and neurological parameters to evaluate neonatal well-being and assess the likelihood and severity of perinatal asphyxia. Furthermore, BE or BD may also assist in guiding therapeutic decisions, such as the initiation of hypothermia therapy for neonates experiencing hypoxic ischemic events [83,86].
Some studies have shown a negative correlation between BD and cerebral tissue oxygenation in fetuses shortly before delivery [38] and in extremely preterm neonates on the first day after birth [72]. Against these, some studies have shown a negative correlation between BE and cerebral tissue oxygenation in neonates and infants suffering from infantile hypertrophic pyloric stenosis in the perioperative setting [69] and in healthy full-term neonates during the first 10 min of extra-uterine life [79]. Finally, one study reported a positive correlation between BE and cerebral tissue oxygenation in preterm and term neonates during the first 15 min after birth [34]. These differences may be due to variations in the number of included neonates, the timing and interval between measurements of acid–base status parameters and cerebral tissue oxygenation, and the clinical setting (e.g., HCO3 administration, surgical procedures).
4.3. Bicarbonate (HCO3) and Cerebral Tissue Oxygenation
HCO3 is a critical predictor of neonatal morbidity, and it is used to correct metabolic acidosis, thereby improving hemodynamic parameters. The benefits and harms of HCO3 administration in neonates are debated in the literature [34,46,63,68,69,72,80]. Three studies analyzed the effect of HCO3 administration on HCO3 levels and cerebral tissue oxygenation [34,69,72], whereby two studies [34,72] found a positive association, while one study [69] reported a negative correlation. These differences may be due to variations in the number of included neonates, the gestational age of the neonates, the timing and interval between measurements of acid–base status parameters and cerebral tissue oxygenation, and the clinical setting (e.g., HCO3 administration, surgical procedures).
4.4. Studies Involving Neonates with Cardiovascular System Impairments
Four studies focused on neonates with congenital heart disease [26,57,64,80]. Except for the study by Amigoni et al. [26], no association was found between acid–base status parameters and cerebral tissue oxygenation in these neonates [57,64,80]. As discussed in the Introduction, the cardiovascular system significantly influences cerebral tissue oxygenation in neonates. Impairments in the cardiovascular system, as observed in neonates with congenital heart diseases, may act as confounders, resulting in potential bias and the absence of observed associations between acid–base status parameters and cerebral tissue oxygenation. This confounding effect might also depend on the severity of congenital malformation, which varied significantly among the included studies. Additionally, two studies [26,57] measured acid–base status parameters and cerebral tissue oxygenation during surgery involving a cardiopulmonary bypass procedure.
4.5. Studies During the Transition from Intra- to Extrauterine Life
The immediate postnatal period is characterized by unique physiological conditions. Studies examining neonates during and immediately after the transition from intra- to extrauterine life have reported both positive and negative correlations between acid–base status parameters and cerebral tissue oxygenation [34,38,79]. Notably, in the study by Aldricht et al. [38], cerebral tissue oxygenation was measured during childbirth prior to the clamping of the umbilical cord. Both Aldricht et al. [38] and Mattersberger et al. [34] found positive correlations between acid–base status parameters and cerebral tissue oxygenation in neonates during delivery and immediately after birth, respectively. In contrast, Leroy et al. [79] found a negative correlation in healthy full-term singleton neonates during uncomplicated transition. Mattersberger et al. [34] observed differences in correlations between preterm and term neonates. These differences suggest that gestational age-related differences may, at least in part, explain the variability in correlations observed across studies investigating the immediate transition after birth.
4.6. Studies on Term and Preterm Neonates
The physiological differences between preterm and term neonates may impact the relationship between acid–base status parameters and cerebral tissue oxygenation. As already mentioned, Mattersberger et al. [34] found associations between capillary measured pH/BE levels and brain oxygenation in preterm neonates, whereas associations between HCO3 and cerebral tissue oxygenation were observed in term neonates. Against them, Dusleag et al. [85] found no associations between the pH/BE/HCO3—measured with respect to the umbilical cord blood—and cerebral tissue oxygenation in preterm neonates with and term neonates without respiratory support during the first 15 min after birth [85]. Unfortunately, no other study compared preterm and full-term neonates. However, some studies included preterm neonates [43,46,63,68,72,74], while others included full-term neonates [75,79,83], yielding controversial results (Table 1, Table 2 and Table 3) that suggest that gestational age has an impact on the influence of acid–base status on cerebral tissue oxygenation.
4.7. Proposed Explanatory Model
4.7.1. pH and Cerebral Oxygenation
Acidosis can reduce the contractility of cardiomyocytes and diminish cardiac responsiveness to catecholamines, which may both lower cardiac output and cerebral oxygen delivery [87]. However, in hemodynamically stable preterm infants, myocardial function remains largely unaffected during the early transitional period, even with markedly low pH levels, and there appears to be no clear relationship between pH and cardiac output in the first three days after birth [88]. The vascular response to acidosis is developmentally regulated. From day 4 to 14 after the transition, systemic vascular resistance decreases and left ventricular output increases, while no association between pH and vascular tone is seen during the first three days [88]. These observations may demonstrate that the effect of pH on vascular tone—and consequently on regional blood flow—is dependent on postnatal age and therefore differs according to postnatal age. In addition, acidosis causes cerebral vasodilation, resulting in increased cerebral blood flow and oxygenation [26]. These effects could explain an increase in cerebral blood supply and, consequently, cerebral oxygenation.
4.7.2. Base Excess (BE) or Base Deficit (BD) and Cerebral Tissue Oxygenation
A possible explanation for the association between BE or BD and cerebral oxygenation is that BE or BD is calculated from the pH value. Furthermore, BE is an indicator of shock, resuscitation efficacy, and volume deficit, and a decreased BE likely indicates centralization, with resulting hemodynamic effects on cerebral oxygen delivery [89,90].
4.7.3. Bicarbonate (HCO3) and Cerebral Tissue Oxygenation
A possible explanation for the correlation between HCO3 and cerebral oxygenation may be the strong link between pH and HCO3 levels. However, a study in healthy males demonstrated that bicarbonate concentration affects cerebral blood flow (CBF) independently of pH and CO2 levels [91].
4.8. Risk-of-Bias Assessment of Studies Describing Correlations Between Parameters of Acid–Base Status and Cerebral Oxygenation
Only one study [79], categorized as “low risk of bias” or “some concerns”, demonstrated a correlation of pH level and BE with cerebral tissue oxygenation in neonates. Six studies [26,34,38,69,72,83], categorized as “high risk” or “very high risk of bias”, also described such an association (Table 5). Using the ROBINS-E tool for risk of bias assessment, the main factors for increased risk of bias were a lack of consideration of confounders, selection bias, post-exposure intervention bias, and missing data (Table 4). In some studies, acid–base status parameters were secondary outcome parameters [57,64,68,75,83,85]. These methodological weaknesses may contribute to the incongruent results regarding potential associations.
5. Conclusions
This review reveals controversial associations between acid–base status parameters and cerebral tissue oxygenation in neonates. The variability in findings can be attributed to heterogeneity in study populations, especially concerning gestational age, timing of measurements, and clinical contexts. However, the studies with the lowest risk of bias mostly demonstrated the absence of association between the acid–base status parameters and cerebral tissue oxygenation, suggesting the need for more consistent methodologies and further research in this area.
Author Contributions
All authors contributed substantially to the conception and design of this study, data acquisition, analysis, and interpretation. Conceptualization, methodology, original draft preparation, writing—review and editing, and validation: C.M., B.S., N.B.-S., and G.P. Data collection and formal analysis: C.M., B.S., N.B.-S., and G.P. Writing review, visualization and editing, and supervision: C.M., B.S., N.B.-S., and G.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created.
Conflicts of Interest
The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Abbreviations
The following abbreviations are used in this manuscript:
| ad. | Administration |
| BD | Base deficit |
| BE | Base excess |
| CDH | Congenital diaphragmatic hernia |
| CO2 | Carbon dioxide |
| CPB | Cardiopulmonary bypass |
| crSO2 | Cerebral regional oxygen saturation |
| EA | Esophageal atresia |
| FTOE | Fractional tissue oxygen extraction |
| HCO3 | Bicarbonate |
| HIE | Hypoxic ischemic encephalopathy |
| IVH | Intraventricular hemorrhage |
| LVO | Left ventricular output |
| min | Minutes |
| NIRS | Near-infrared spectroscopy |
| n.r | Not reported |
| PA | Perinatal asphyxia; |
| PH-IVH | Pulmonary and intraventricular hemorrhage |
| PVL | Periventricular leukomalacia |
| RBC | Red blood cell |
| RVO | Right ventricular output |
| U.A. | Umbilical artery |
| U.V. | Umbilical venous |
References
- Handley, S.C.; Passarella, M.; Lee, H.C.; Lorch, S.A. Incidence Trends and Risk Factor Variation in Severe Intraventricular Hemorrhage across a Population Based Cohort Sara. J. Pediatr. 2018, 200, 24–29.e3. [Google Scholar] [CrossRef] [Scilit]
- Tzeng, Y.-C.; Ainslie, P.N. Blood pressure regulation IX: Cerebral autoregulation under blood pressure challenges. Eur. J. Appl. Physiol. 2014, 114, 545–559. [Google Scholar] [CrossRef] [Scilit]
- Badurdeen, S.; Roberts, C.; Blank, D.; Miller, S.; Stojanovska, V.; Davis, P.; Hooper, S.; Polglase, G. Haemodynamic instability and brain injury in neonates exposed to Hypoxia–Ischaemia. Brain Sci. 2019, 9, 49. [Google Scholar] [CrossRef] [Scilit]
- Shukla, V.V.; Klinger, A.; Yazdi, S.; Rahman, A.K.M.F.; Wright, S.; Barganier, A.; Ambalavanan, N.; Carlo, W.A.; Ramani, M. Prevention of severe brain injury in very preterm neonates: A quality improvement initiative. J. Perinatol. 2022, 42, 1417–1423. [Google Scholar] [CrossRef] [Scilit]
- Greisen, G. Autoregulation of cerebral blood flow in newborn babies. Early Hum. Dev. 2005, 81, 423–428. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yiş, U.; Kurul, S.H.; Kumral, A.; Cilaker, S.; Tuğyan, K.; Genç, Ş.; Yılmaz, O. Hyperoxic exposure leads to cell death in the developing brain. Brain Dev. 2008, 30, 556–562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Plomgaard, A.M.; Alderliesten, T.; Austin, T.; van Bel, F.; Benders, M.; Claris, O.; Dempsey, E.; Fumagalli, M.; Gluud, C.; Hagmann, C.; et al. Early biomarkers of brain injury and cerebral hypo- and hyperoxia in the SafeBoosC II trial. PLoS ONE 2017, 12, e0173440. [Google Scholar] [CrossRef] [Scilit]
- Davis, P.G.; Tan, A.; O’Donnell, C.P.; Schulze, A. Resuscitation of newborn infants with 100% oxygen or air: A systematic review and meta-analysis. Lancet 2000, 364, 1329–1333. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leijser, L.M.; de Vries, L.S. Preterm brain injury: Germinal matrix–intraventricular hemorrhage and post-hemorrhagic ventricular dilatation. In Handbook of Clinical Neurology; Elsevier B.V.: Amsterdam, The Netherlands, 2019; Volume 162, pp. 173–199. [Google Scholar]
- Mukerji, A.; Shah, V.; Shah, P.S. Periventricular/Intraventricular Hemorrhage and Neurodevelopmental Outcomes: A Meta-analysis. Pediatrics 2015, 136, 1132–1143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vergani, P.; Locatelli, A.; Doria, V.; Assi, F.; Paterlini, G.; Pezzullo, J.C.; Ghidini, A. Intraventricular hemorrhage and periventricular leukomalacia in preterm infants. Obstet. Gynecol. 2004, 104, 225–231. [Google Scholar] [CrossRef] [Scilit]
- O’Donnell, C.P.F.; Kamlin, C.O.F.; Davis, P.G.; Morley, C.J. Feasibility of and delay in obtaining pulse oximetry during neonatal resuscitation. J. Pediatr. 2005, 147, 698–699. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Finer, N.; Leone, T. Oxygen saturation monitoring for the preterm infant: The evidence basis for current practice. Pediatr. Res. 2009, 65, 375–380. [Google Scholar] [CrossRef] [Scilit]
- Dawson, J.A.; Morley, C.J. Monitoring oxygen saturation and heart rate in the early neonatal period. Semin. Fetal Neonatal Med. 2010, 15, 203–207. [Google Scholar] [CrossRef] [Scilit]
- Baik, N.; Urlesberger, B.; Schwaberger, B.; Schmölzer, G.M.; Avian, A.; Pichler, G. Cerebral haemorrhage in preterm neonates: Does cerebral regional oxygen saturation during the immediate transition matter? Arch. Dis. Child. Fetal Neonatal Ed. 2015, 100, F422–F427. [Google Scholar] [CrossRef] [Scilit]
- Hyttel-Sorensen, S.; Greisen, G.; Als-Nielsen, B.; Gluud, C. Cerebral near-infrared spectroscopy monitoring for prevention of brain injury in very preterm infants. Cochrane Database Syst. Rev. 2017, 9, CD011506. [Google Scholar] [CrossRef] [Scilit]
- Suppan, E.; Pichler, G.; Binder-Heschl, C.; Schwaberger, B.; Urlesberger, B. Three Physiological Components That Influence Regional Cerebral Tissue Oxygen Saturation. Front. Pediatr. 2022, 10, 913223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martini, S.; Thewissen, L.; Austin, T.; da Costa, C.S.; de Boode, W.P.; Dempsey, E.; Kooi, E.; Pellicer, A.; Rhee, C.J.; Riera, J.; et al. Near-infrared spectroscopy monitoring of neonatal cerebrovascular reactivity: Where are we now? Pediatr. Res. 2023, 96, 884–895. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tian, F.; Tarumi, T.; Liu, H.; Zhang, R.; Chalak, L. Wavelet coherence analysis of dynamic cerebral autoregulation in neonatal hypoxic-ischemic encephalopathy. NeuroImage Clin. 2016, 11, 124–132. [Google Scholar] [CrossRef] [Scilit]
- Pichler, G.; Urlesberger, B.; Baik, N.; Schwaberger, B.; Binder-Heschl, C.; Avian, A.; Pansy, J.; Cheung, P.-Y.; Schmölzer, G.M. Cerebral Oxygen Saturation to Guide Oxygen Delivery in Preterm Neonates for the Immediate Transition after Birth: A 2-Center Randomized Controlled Pilot Feasibility Trial. J. Pediatr. 2016, 170, 73–78.e4. [Google Scholar] [CrossRef] [Scilit]
- Richmond, S.; Wyllie, J. European Resuscitation Council Guidelines for Resuscitation 2010. Section 7. Resuscitation of babies at birth. Resuscitation 2010, 81, 1389–1399. [Google Scholar] [CrossRef] [Scilit]
- Pellicer, A.; Greisen, G.; Benders, M.; Claris, O.; Dempsey, E.; Fumagalli, M.; Gluud, C.; Hagmann, C.; Hellström-Westas, L.; Hyttel-Sorensen, S.; et al. The SafeBoosC phase II randomised clinical trial: A treatment guideline for targeted near-infrared-derived cerebral tissue oxygenation versus standard treatment in extremely preterm infants. Neonatology 2013, 104, 171–178. [Google Scholar] [CrossRef] [Scilit]
- Hankins, G.D.V.; Speer, M. Defining the Pathogenesis and Pathophysiology of Neonatal Encephalopathy and Cerebral Palsy. Obstet. Gynecol. 2003, 102, 628–636. [Google Scholar]
- Lin, Z.L.; Yu, H.M.; Lin, J.; Chen, S.Q.; Liang, Z.Q.; Zhang, Z.Y. Mild hypothermia via selective head cooling as neuroprotective therapy in term neonates with perinatal asphyxia: An experience from a single neonatal intensive care unit. J. Perinatol. 2006, 26, 180–184. [Google Scholar] [CrossRef] [Scilit]
- Ferreira, C.S.; Melo, Â.; Fachada, A.H.; Solheiro, H.; Nogueira Martins, N. Umbilical Cord Blood Gas Analysis, Obstetric Performance and Perinatal Outcome. Rev. Bras. Ginecol. Obstet. 2018, 40, 740–748. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amigoni, A.; Mozzo, E.; Brugnaro, L.; Tiberio, I.; Pittarello, D.; Stellin, G.; Bonato, R. Four-side near-infrared spectroscopy measured in a paediatric population during surgery for congenital heart disease. Interact. Cardiovasc. Thorac. Surg. 2011, 12, 707–712. [Google Scholar] [CrossRef] [Scilit]
- Andres, R.; Saade, G.; Gilstrap, L.; Wilkins, I.; Witlin, A.; Zlatnik, F.; Hankins, G. Association between umbilical blood gas parameters and neonatal morbidity and death in neonates with pathologic fetal acidemia. Am. J. Obstet. Gynecol. 1999, 181, 867–871. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ACOG Committee on Obstetric Practice. ACOG Committee Opinion No. 348: Umbilical cord blood gas and acid-base analysis. Obstet. Gynecol. 2006, 108, 1319–1322. [Google Scholar] [CrossRef] [Scilit]
- Levene, M.I.; Fawer, C.-L.; Lamont, R.F. Risk factors in the development of intraventricular haemorrhage in the preterm neonate. Arch. Dis. Child. 1982, 57, 410–417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yli, B.M.; Kjellmer, I. Pathophysiology of foetal oxygenation and cell damage during labour. Best. Pr. Res. Clin. Obstet. Gynaecol. 2016, 30, 9–21. [Google Scholar] [CrossRef] [Scilit]
- Olofsson, P. Umbilical cord pH, blood gases, and lactate at birth: Normal values, interpretation, and clinical utility. Am. J. Obstet. Gynecol. 2023, 228, S1222–S1240. [Google Scholar] [CrossRef] [Scilit]
- Buckley, E.M.; Naim, M.Y.; Lynch, J.M.; Goff, D.A.; Schwab, P.J.; Diaz, L.K.; Nicolson, S.C.; Montenegro, L.M.; Lavin, N.A.; Durduran, T.; et al. Sodium bicarbonate causes dose-dependent increases in cerebral blood flow in infants and children with single ventricle physiology. Pediatr. Res. 2013, 73, 668–673. [Google Scholar] [CrossRef] [Scilit]
- Matterberger, C.; Baik-Schneditz, N.; Schwaberger, B.; Schmölzer, G.M.; Mileder, L.; Pichler-Stachl, E.; Urlesberger, B.; Pichler, G. Blood Glucose and Cerebral Tissue Oxygenation Immediately after Birth—An Observational Study. J. Pediatr. 2018, 200, 19–23. [Google Scholar] [CrossRef] [Scilit]
- Mattersberger, C.; Baik-Schneditz, N.; Schwaberger, B.; Schmölzer, G.M.; Mileder, L.; Urlesberger, B.; Pichler, G. Acid-base and metabolic parameters and cerebral oxygenation during the immediate transition after birth—A two-center observational study. PLoS ONE 2023, 18, e0283278. [Google Scholar] [CrossRef] [Scilit]
- Mattersberger, C.; Schmölzer, G.M.; Urlesberger, B.; Pichler, G. Blood Glucose and Lactate Levels and Cerebral Oxygenation in Preterm and Term Neonates—A Systematic Qualitative Review of the Literature. Front. Pediatr. 2020, 8, 361. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. Syst Rev. 2021, 10, 89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bero, L.; Chartres, N.; Diong, J.; Fabbri, A.; Ghersi, D.; Lam, J.; Lau, A.; McDonald, S.; Mintzes, B.; Sutton, P.; et al. The risk of bias in observational studies of exposures (ROBINS-E) tool: Concerns arising from application to observational studies of exposures. Syst. Rev. 2018, 7, 242. [Google Scholar] [CrossRef] [Scilit]
- Aldrich, C.J.; D’Antona, D.; Wyatt, J.S.; A Spencer, J.; Peebles, D.M.; O Reynolds, E. Fetal cerebral oxygenation measured by near-infrared spectroscopy shortly before birth and acid-base status at birth. Obstet. Gynecol. 1994, 50, 116–117. [Google Scholar]
- Naulaers, G. Cerebral tissue oxygenation index in very premature infants. Arch. Dis. Child.-Fetal Neonatal Ed. 2002, 87, F189–F192. [Google Scholar] [CrossRef] [Scilit]
- Ramamoorthy, C.; Tabbutt, S.; Kurth, C.D.; Steven, J.M.; Montenegro, L.M.; Durning, S.; Wernovsky, G.; Gaynor, J.W.; Spray, T.L.; Nicolson, S.C. Effects of Inspired Hypoxic and Hypercapnic Gas Mixtures on Cerebral Oxygen Saturation in Neonates with Univentricular Heart Defects. Anesthesiology 2002, 96, 283–288. [Google Scholar] [CrossRef] [Scilit]
- Andropoulos, D.B.; Stayer, S.A.; McKenzie, E.D.; Fraser, C.D.; Pigula, F.A.; Austin, E.H. Novel cerebral physiologic monitoring to guide low-flow cerebral perfusion during neonatal aortic arch reconstruction. J. Thorac. Cardiovasc. Surg. 2003, 125, 491–499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naulaers, G.; Morren, G.; Van Huffel, S.; Casaer, P.; Devlieger, H. Measurement of tissue oxygenation index during the first three days in premature born infants. Adv. Exp. Med. Biol. 2003, 510, 379–383. [Google Scholar]
- von Siebenthal, K.; Keel, M.; Fauchère, J.C.; Dietz, V.; Haensse, D.; Wolf, U.; Helfenstein, U.; Bänziger, O.; Bucher, H.U.; Wolf, M. Variability of Cerebral Hemoglobin Concentration in Very Preterm Infants During the First 6 Hours of Life. Adv. Exp. Med. Biol. 2005, 566, 91–97. [Google Scholar] [PubMed]
- Weiss, M.; Dullenkopf, A.; Kolarova, A.; Schulz, G.; Frey, B.; Baenziger, O. Near-infrared spectroscopic cerebral oxygenation reading in neonates and infants is associated with central venous oxygen saturation. Paediatr. Anaesth. 2005, 15, 102–109. [Google Scholar] [CrossRef] [Scilit]
- Victor, S.; Appleton, R.E.; Beirne, M.; Marson, A.G.; Weindling, A.M. Effect of carbon dioxide on background cerebral electrical activity and fractional oxygen extraction in very low birth weight infants just after birth. Pediatr. Res. 2005, 58, 579–585. [Google Scholar] [CrossRef] [Scilit]
- van Alfen-van Der Velden, A.A.E.M.; Hopman, J.C.W.; Klaessens, J.H.G.M.; Feuth, T.; Sengers, R.C.A.; Liem, K.D. Effects of Rapid versus Slow Infusion of Sodium Bicarbonate on Cerebral Hemodynamics and Oxygenation in Preterm Infants. Biol. Neonate. 2006, 90, 122–127. [Google Scholar] [CrossRef] [Scilit]
- Zaramella, P.; Freato, F.; Quaresima, V.; Ferrari, M.; Bartocci, M.; Rubino, M.; Falcon, E.; Chiandetti, L. Surgical closure of patent ductus arteriosus reduces the cerebral tissue oxygenation index in preterm infants: A near-infrared spectroscopy and Doppler study. Pediatr. Int. 2006, 48, 305–312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Victor, S.; Appleton, R.E.; Beirne, M.; Marson, A.G.; Weindling, A.M. The relationship between cardiac output, cerebral electrical activity, cerebral fractional oxygen extraction and peripheral blood flow in premature newborn infants. Pediatr. Res. 2006, 60, 456–460. [Google Scholar] [CrossRef] [Scilit]
- Zaramella, P.; Saraceni, E.; Freato, F.; Falcon, E.; Suppiej, A.; Milan, A.; Laverda, A.M.; Chiandetti, L. Can tissue oxygenation index (TOI) and cotside neurophysiological variables predict outcome in depressed/asphyxiated newborn infants? Early Hum. Dev. 2007, 83, 483–489. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Horvath, R.; Shore, S.; Schultz, S.E.; Rosenkranz, E.R.; Cousins, M.; Ricci, M. Cerebral and somatic oxygen saturation decrease after delayed sternal closure in children after cardiac surgery. J. Thorac. Cardiovasc. Surg. 2010, 139, 894–900. [Google Scholar] [CrossRef] [Scilit]
- Bishay, M.; Giacomello, L.; Retrosi, G.; Thyoka, M.; Nah, S.A.; McHoney, M.; De Coppi, P.; Brierley, J.; Scuplak, S.; Kiely, E.M.; et al. Decreased cerebral oxygen saturation during thoracoscopic repair of congenital diaphragmatic hernia and esophageal atresia in infants. J. Pediatr. Surg. 2011, 46, 47–51. [Google Scholar] [CrossRef] [Scilit]
- Gunaydin, B.; Nas, T.; Biri, A.; Koc, E.; Koc, A.; McCusker, K. Effects of maternal supplementary oxygen on the newborn for elective cesarean deliveries under spinal anesthesia. J. Anesth. 2011, 25, 363–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Redlin, M.; Huebler, M.; Boettcher, W.; Kukucka, M. Minimizing intraoperative hemodilution by use of a very low priming volume cardiopulmonary bypass in neonates with transposition of the great arteries. J. Thorac. Cardiovasc. Surg. 2011, 142, 875–881. [Google Scholar] [CrossRef] [Scilit]
- Bravo, M.D.C.; López, P.; Cabañas, F.; Pérez-Rodríguez, J.; Pérez-Fernández, E.; Pellicer, A. Acute effects of levosimendan on cerebral and systemic perfusion and oxygenation in newborns: An observational study. Neonatology 2011, 99, 217–223. [Google Scholar] [CrossRef] [Scilit]
- Quarti, A.; Manfrini, F.; Oggianu, A.; D’ORfeo, F.; Genova, S.; Silvano, R.; Pozzi, M. Non-invasive cerebral oximetry monitoring during cardiopulmonary bypass in congenital cardiac surgery: A starting point. Perfusion 2011, 26, 289–293. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quarti, A.; Nardone, S.; Manfrini, F.; D’oRfeo, F.; Genova, S.; Silvano, R.; Pozzi, M. Effect of the adjunct of carbon dioxide during cardiopulmonary bypass on cerebral oxygenation. Perfusion 2013, 28, 152–155. [Google Scholar] [CrossRef] [Scilit]
- Menke, J.; Möller, G. Cerebral near-infrared spectroscopy correlates to vital parameters during cardiopulmonary bypass surgery in children. Pediatr. Cardiol. 2013, 35, 155–163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pellicer, A.; Riera, J.; Lopez-Ortego, P.; Bravo, M.C.; Madero, R.; Perez-Rodriguez, J.; Labrandero, C.; Quero, J.; Buño, A.; Castro, L.; et al. Phase 1 study of two inodilators in neonates undergoing cardiovascular surgery. Pediatr. Res. 2013, 73, 95–103. [Google Scholar] [CrossRef] [Scilit]
- Conforti, A.; Giliberti, P.; Mondi, V.; Valfré, L.; Sgro, S.; Picardo, S.; Bagolan, P.; Dotta, A. Near infrared spectroscopy: Experience on esophageal atresia infants. J. Pediatr. Surg. 2014, 49, 1064–1068. [Google Scholar] [CrossRef] [Scilit]
- Mintzer, J.P.; Parvez, B.; Chelala, M.; Alpan, G.; Lagamma, E.F. Monitoring regional tissue oxygen extraction in neonates <1250 g helps identify transfusion thresholds independent of hematocrit. J. Neonatal Perinatal Med. 2014, 7, 89–100. [Google Scholar]
- Kim, J.W.; Shin, W.J.; Park, I.; Chung, I.S.; Gwak, M.; Hwang, G.S. Splanchnic oxygen saturation immediately after weaning from cardiopulmonary bypass can predict early postoperative outcomes in children undergoing congenital heart surgery. Pediatr. Cardiol. 2014, 35, 587–595. [Google Scholar] [CrossRef] [Scilit]
- Gupta, P.; McDonald, R.; Goyal, S.; Gossett, J.M.; Imamura, M.; Agarwal, A.; Butt, W.; Bhutta, A.T. Extubation failure in infants with shunt-dependent pulmonary blood flow and univentricular physiology. Cardiol. Young 2014, 24, 64–72. [Google Scholar] [CrossRef] [Scilit]
- Mintzer, J.P.; Parvez, B.; Alpan, G.; LaGamma, E.F. Effects of sodium bicarbonate correction of metabolic acidosis on regional tissue oxygenation in very low birth weight neonates. J. Perinatol. 2015, 35, 601–606. [Google Scholar] [CrossRef] [Scilit]
- Mebius, M.J.; van der Laan, M.E.; Verhagen, E.A.; Roofthooft, M.T.; Bos, A.F.; Kooi, E.M. Cerebral oxygen saturation during the first 72h after birth in infants diagnosed prenatally with congenital heart disease. Early Hum. Dev. 2016, 103, 199–203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tytgat, S.H.A.J.; van Herwaarden, M.Y.A.; Stolwijk, L.J.; Keunen, K.; Benders, M.J.N.L.; de Graaff, J.C.; Milstein, D.M.J.; van der Zee, D.C.; Lemmers, P.M.A. Neonatal brain oxygenation during thoracoscopic correction of esophageal atresia. Surg. Endosc. Other Interv. Tech. 2015, 30, 2811–2817. [Google Scholar] [CrossRef] [Scilit]
- Torre, S.; Biondani, E.; Menon, T.; Marchi, D.; Franzoi, M.; Ferrarini, D.; Tabbì, R.; Hoxha, S.; Barozzi, L.; Faggian, G.; et al. Continuous Metabolic Monitoring in Infant Cardiac Surgery: Toward an Individualized Cardiopulmonary Bypass Strategy. Artif. Organs. 2016, 40, 65–72. [Google Scholar] [CrossRef] [Scilit]
- Dix, L.M.L.; Weeke, L.C.; de Vries, L.S.; Groenendaal, F.; Baerts, W.; van Bel, F.; Lemmers, P.M.A. Carbon Dioxide Fluctuations Are Associated with Changes in Cerebral Oxygenation and Electrical Activity in Infants Born Preterm. J. Pediatr. 2017, 187, 66–72.e1. [Google Scholar] [CrossRef] [Scilit]
- Hunter, C.L.; Oei, J.L.; Lui, K.; Schindler, T. Cerebral oxygenation as measured by Near-Infrared Spectroscopy in neonatal intensive care: Correlation with arterial oxygenation. Acta Paediatr. 2017, 106, 1073–1078. [Google Scholar] [CrossRef] [Scilit]
- Nissen, M.; Cernaianu, G.; Thränhardt, R.; Vahdad, M.R.; Barenberg, K.; Tröbs, R.-B. Does metabolic alkalosis influence cerebral oxygenation in infantile hypertrophic pyloric stenosis. J. Surg. Res. 2017, 212, 229–237. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neunhoeffer, F.; Warmann, S.W.; Hofbeck, M.; Müller, A.; Fideler, F.; Seitz, G.; Schuhmann, M.U.; Kirschner, H.; Kumpf, M.; Fuchs, J. Elevated intrathoracic CO2 pressure during thoracoscopic surgery decreases regional cerebral oxygen saturation in neonates and infants-A pilot study. Paediatr. Anaesth. 2017, 27, 752–759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weeke, L.C.; Dix, L.M.L.; Groenendaal, F.; A Lemmers, P.M.; Dijkman, K.P.; Andriessen, P.; de Vries, L.S.; Toet, M.C. Severe hypercapnia causes reversible depression of aEEG background activity in neonates: An observational study. Arch. Dis. Child. Fetal Neonatal Ed. 2017, 102, F383–F388. [Google Scholar] [CrossRef] [Scilit]
- Katheria, A.C.; Brown, M.K.; Hassan, K.; Poeltler, D.M.; A Patel, D.; Brown, V.K.; Sauberan, J.B. Hemodynamic effects of sodium bicarbonate administration. J. Perinatol. 2017, 37, 518–520. [Google Scholar] [CrossRef] [Scilit]
- Mukai, M.; Uchida, T.; Itoh, H.; Suzuki, H.; Niwayama, M.; Kanayama, N. Tissue oxygen saturation levels from fetus to neonate. J. Obstet. Gynaecol. Res. 2017, 43, 855–859. [Google Scholar] [CrossRef] [Scilit]
- Janaillac, M.; Beausoleil, T.P.; Barrington, K.J.; Raboisson, M.-J.; Karam, O.; Dehaes, M.; Lapointe, A. Correlations between near-infrared spectroscopy, perfusion index, and cardiac outputs in extremely preterm infants in the first 72 h of life. Eur. J. Pediatr. 2018, 177, 541–550. [Google Scholar] [CrossRef] [Scilit]
- Mebius, M.; Verhagen, E.; van der Laan, M.; Bos, A. Cerebral oxygen saturation and extraction in neonates with persistent pulmonary hypertension during the first 72 hours of life. Arch. Dis. Child. 2012, 97, A481–A482. [Google Scholar] [CrossRef] [Scilit]
- Polavarapu, S.R.; Fitzgerald, G.D.; Contag, S.; Hoffman, S.B. Utility of prenatal Doppler ultrasound to predict neonatal impaired cerebral autoregulation. J. Perinatol. 2018, 38, 474–481. [Google Scholar] [CrossRef] [Scilit]
- Beausoleil, T.P.; Janaillac, M.; Barrington, K.J.; Lapointe, A.; Dehaes, M. Cerebral oxygen saturation and peripheral perfusion in the extremely premature infant with intraventricular and/or pulmonary haemorrhage early in life. Sci. Rep. 2018, 8, 6511. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Costerus, S.; Vlot, J.; Van Rosmalen, J.; Wijnen, R.; Weber, F. Effects of Neonatal Thoracoscopic Surgery on Tissue Oxygenation: A Pilot Study on (Neuro-) Monitoring and Outcomes. Eur. J. Pediatr. Surg. 2019, 29, 166–172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leroy, L.; Mahmoudzadeh, M.; Gondry, J.; Foulon, A.; Wallois, F. Dynamics of cortical oxy genation during immediate adaptation to extrauterine life. Sci. Rep. 2021, 11, 22041. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loomba, R.S.; Villarreal, E.G.; Dyamenahalli, U.; Farias, J.S.; Flores, S. Acute Effects of Sodium Bicarbonate in Children with Congenital Heart Disease with Biventricular Circulation in Non-cardiac Arrest Situations. Pediatr. Cardiol. 2022, 43, 1723–1727. [Google Scholar] [CrossRef] [Scilit]
- Knieling, F.; Cesnjevar, R.; Regensburger, A.P.; Wagner, A.L.; Purbojo, A.; Dittrich, S.; Münch, F.; Neubert, A.; Woelfle, J.; Jüngert, J.; et al. Transfontanellar Contrast-enhanced US for Intraoperative Imaging of Cerebral Perfusion during Neonatal Arterial Switch Operation. Radiology 2022, 304, 164–173. [Google Scholar] [CrossRef] [Scilit]
- Savorgnan, F.; Loomba, R.S.; Flores, S.; Rusin, C.G.; Zheng, F.; Hassan, A.M.; Acosta, S. Descriptors of Failed Extubation in Norwood Patients Using Physiologic Data Streaming. Pediatr. Cardiol. 2023, 44, 396–403. [Google Scholar] [CrossRef] [Scilit]
- Kazanasmaz, H.; Akan, A.; Yalçın, Ö.; Ölçücü, M.T.; Onar, S.; Kazanasmaz, Ö. Cerebral Tissue Oxygen Saturation Measurements in Perinatal Asphyxia Cases Treated with Therapeutic Hypothermia. Ther. Hypothermia Temp. Manag. 2023, 13, 184–190. [Google Scholar] [CrossRef] [Scilit]
- Cheng, K.; Zhu, H.; Zhou, Z.; Chen, W.; Yang, A. Value of brain tissue oxygen saturation in neonatal respiratory distress syndrome: A clinical study. Eur. J. Transl. Myol. 2024, 34, 11863. [Google Scholar] [CrossRef] [Scilit]
- Dusleag, M.; Urlesberger, B.; Schwaberger, B.; Baik-Schneditz, N.; Schlatzer, C.; Wolfsberger, C.H.; Pichler, G. Acid base and metabolic parameters of the umbilical cord blood and cerebral oxygenation immediately after birth. Front. Pediatr. 2024, 12, 1385726. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Low, J.A.; Galbraith, R.S.; Raymond, M.J.; Derrick, E.J. Cerebral blood flow velocity in term newborns following intrapartum fetal asphyxia. Acta Paediatr. Int. J. Paediatr. 1994, 83, 1012–1016. [Google Scholar] [CrossRef] [Scilit]
- Marsh, J.D.; Margolis, T.I.; Kim, D. Mechanism of diminished contractile response to catecholamines during acidosis. Am. J. Physiol.-Heart Circ. Physiol. 1988, 254, H20–H27. [Google Scholar] [CrossRef] [Scilit]
- Noori, S.; Wu, T.W.; Seri, I. PH effects on cardiac function and systemic vascular resistance in preterm infants. J. Pediatr. 2013, 162, 958–963.e1. [Google Scholar] [CrossRef] [Scilit]
- Wiberg, N.; Källén, K.; Olofsson, P. Base deficit estimation in umbilical cord blood is influenced by gestational age, choice of fetal fluid compartment, and algorithm for calculation. Am. J. Obstet. Gynecol. 2006, 195, 1651–1656. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, J.W.; Shackford, S.R.; Holbrook, T.L. Base deficit as a sensitive indicator of compensated shock and tissue oxygen utilization. Surg. Gynecol. Obstet. 1991, 173, 473–476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Caldwell, H.G.; Howe, C.A.; Chalifoux, C.J.; Hoiland, R.L.; Carr, J.M.J.R.; Brown, C.V.; Patrician, A.; Tremblay, J.C.; Panerai, R.B.; Robinson, T.G.; et al. Arterial carbon dioxide and bicarbonate rather than pH regulate cerebral blood flow in the setting of acute experimental metabolic alkalosis. J. Physiol. 2021, 599, 1439–1457. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).