


Featured Application
This study provides a clinical series of colorectal procedures performed with the Hugo™ RAS system. The data demonstrate the platform’s feasibility and safety across a wide spectrum of colorectal resections, including complex rectal cases. The findings support the progressive integration of the Hugo™ RAS system in minimally invasive colorectal surgery programs and contribute to the validation of its technical performance, learning curve, and perioperative outcomes in comparison with established robotic and laparoscopic platforms.
Abstract
Background: Robotic surgery represents the most advanced evolution of minimally invasive colorectal procedures. The Hugo™ Robotic-Assisted Surgery (RAS) platform by Medtronic, introduced in 2021, is a novel modular system designed to enhance accessibility and flexibility. Evidence on its application in colorectal procedures remains limited. This study aimed to evaluate the perioperative outcomes of major colorectal resections performed using the Hugo™ RAS system. Methods: A retrospective, consecutive, single-center case series was conducted on all adult patients who underwent major colorectal surgery using the Hugo™ RAS platform between May 2024 and March 2025. Primary endpoints included operative time, docking time, conversions, and intraoperative complications. Secondary endpoints included postoperative complications (classified using Clavien–Dindo), length of stay, time to bowel function recovery, postoperative pain, and readmission. All perioperative variables were standardized with defined measurement criteria, and complication severity was systematically graded. Results: Forty-four patients were included. All surgeries were completed robotically without conversion or intraoperative complications. The median docking time was 11 min, the median console time was 179 min, and the median operative time was 300 min. Four patients (9.1%) developed major complications (Clavien–Dindo III). Right colectomy anastomoses were intracorporeal, performed with a laparoscopic linear stapler through the assistant port due to absence of a robotic stapler. Conclusions: Major colorectal resections performed with the Hugo™ RAS platform were feasible and safe, with satisfactory perioperative outcomes and no conversions. These findings confirm the reproducibility of this novel robotic system in colorectal surgery. Larger prospective multicenter studies with extended follow-up are warranted to further assess long-term and oncological outcomes.
1. Introduction
Surgery is today one of the best treatment options for both colorectal cancer and benign bowel disease. Colorectal cancer is the 4th most common cancer worldwide and the 5th leading cause of death, so the number of colorectal procedures is expected to increase. Similarly, management of inflammatory bowel disease and diverticulitis often requires surgery, especially in more complex cases or after failure of conservative treatment [1,2]. Laparoscopic surgery has now become widely established as a standard of care across many specialties, with colorectal surgery being one of its predominant applications [3]. However, working in narrow spaces such as the pelvis or performing precise dissection in inflamed, adherent tissues can be technically demanding with a purely laparoscopic approach and may require extensive training.
Among minimally invasive surgical techniques, robotic surgery proposes to overcome these difficulties mainly through enhanced maneuverability of instruments, magnified visualization of the operative field, and improved surgeon comfort [4]. As a result, the integration of robotic platforms in surgical practice represents the most recent and advanced frontier in minimally invasive surgery.
In the last decade, robotic systems have gained a consolidated role in colorectal surgery, particularly for rectal procedures, where their precision and stability significantly improve dissection in deep and confined spaces. Despite these advantages, most of the evidence has been generated using a single robotic platform (Da Vinci®, (Sunnyvale, CA, USA), limiting the comparative evaluation of emerging systems [5].
The Hugo™ RAS platform (Medtronic, Minneapolis, MN, USA), introduced in 2021, is one of the most recent and promising technologies aimed at expanding accessibility and versatility of robotic-assisted surgery. Its modular architecture, open-console design, and independent-arm configuration provide an alternative ergonomic model that could promote greater flexibility and cost efficiency [6].
However, because of the recent introduction of this technology, intraoperative performance and data on perioperative outcomes in colorectal surgery are still limited. Preliminary series have demonstrated feasibility and safety, yet evidence from larger and standardized experiences remains necessary to validate the system in complex colorectal procedures and to define its learning curve [7,8].
Therefore, the aim of this study is to report single-centre experiences and to analyze the perioperative outcomes of major colorectal resections performed using the Hugo™ RAS system, highlighting technical aspects, short-term results, and the early institutional learning curve.
2. Materials and Methods
This retrospective, single-center study included all consecutive adult patients (≥18 years) undergoing major colorectal surgery with the Hugo™ RAS platform from May 2024 to March 2025 at the UOC Chirurgia Colorettale of Fondazione Policlinico Universitario Campus Bio Medico, Rome, Italy, with no preselection based on anatomical difficulty or disease stage. All patients gave written informed consent for inclusion in research protocols. We defined as primary endpoint: perioperative outcomes of major colorectal resections (operative time, docking time, intraoperative complications, conversion) and secondary endpoints: 30-day postoperative complications (Clavien–Dindo), length of stay, blood loss, bowel function recovery. Inclusion criteria: (1) diagnosis of benign or malignant colorectal disease; (2) robotic surgical approach; (3) elective surgery; (4) age ≥ 18 yrs. Exclusion criteria: (1) palliative procedures; (2) emergency surgeries. No patient was excluded based on anatomical complexity, tumor stage, BMI, or previous abdominal surgery. All patients underwent the same preoperative assessment. For oncologic cases, staging was done via clinical, endoscopic and radiological assessment; pathological staging followed the 8th edition of the American Joint Committee on Cancer (AJCC) system [9]. For non-oncologic cases, surgical indication was based on the most recent guidelines. All cases were reviewed in a multidisciplinary team meeting. No specific institutional guideline was used to select patients for robotic resection, the decision for a robotic approach was determined by robotic technology availability and operating room scheduling.
Port placement and robotic arm configuration were customized for each type of procedure as follows:
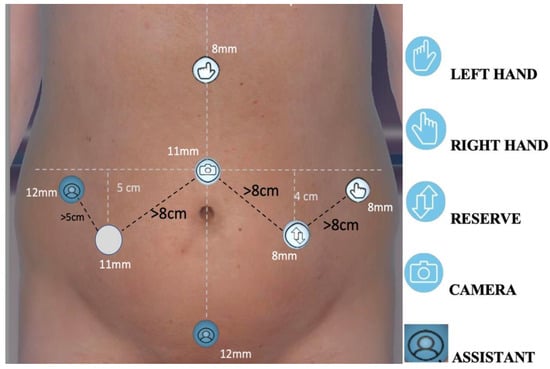
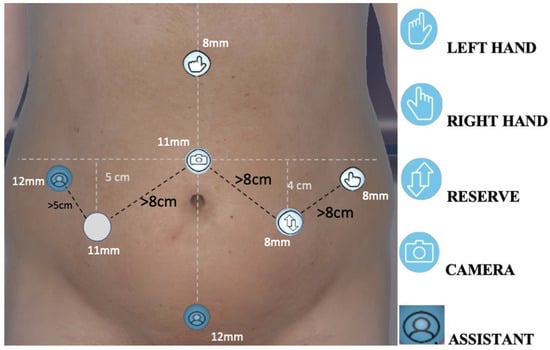
- Splenic flexure resection: 5 ports; 11 mm supra-umbilical robotic port; three 8 mm robotic ports (two in the left flank, one epigastric); an additional 12 mm laparoscopic assistant port in the suprapubic area (Figure 1)
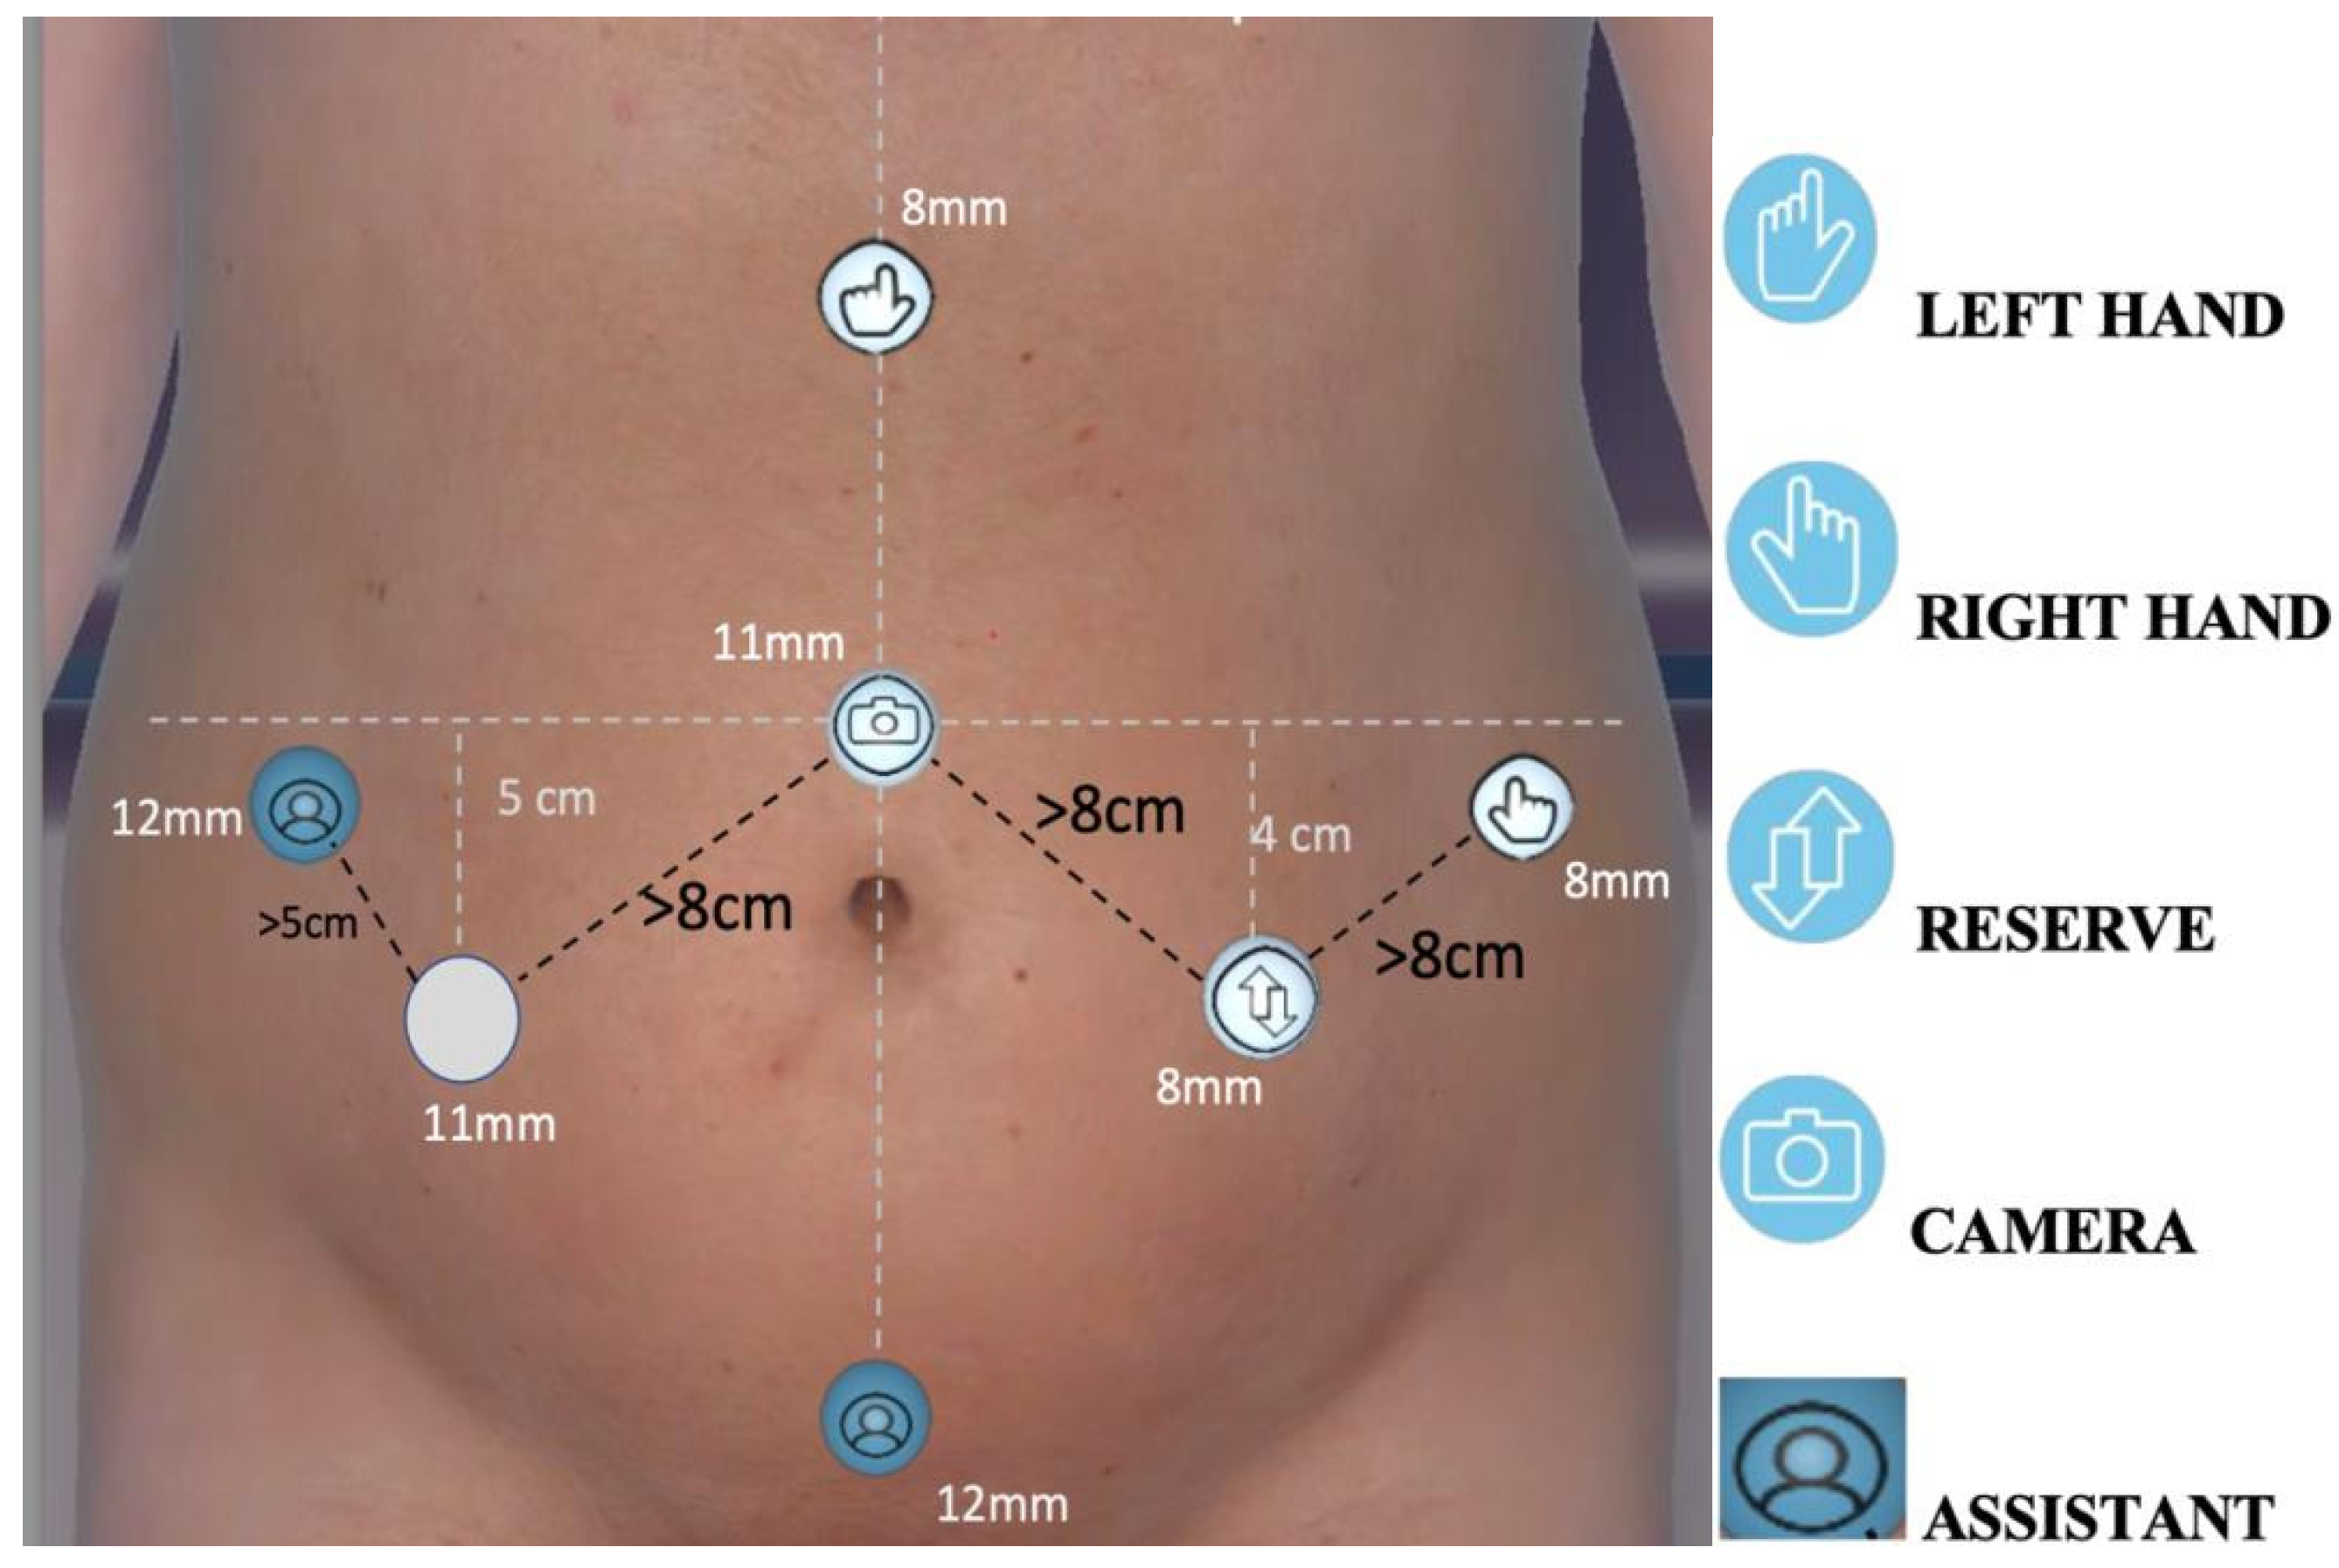
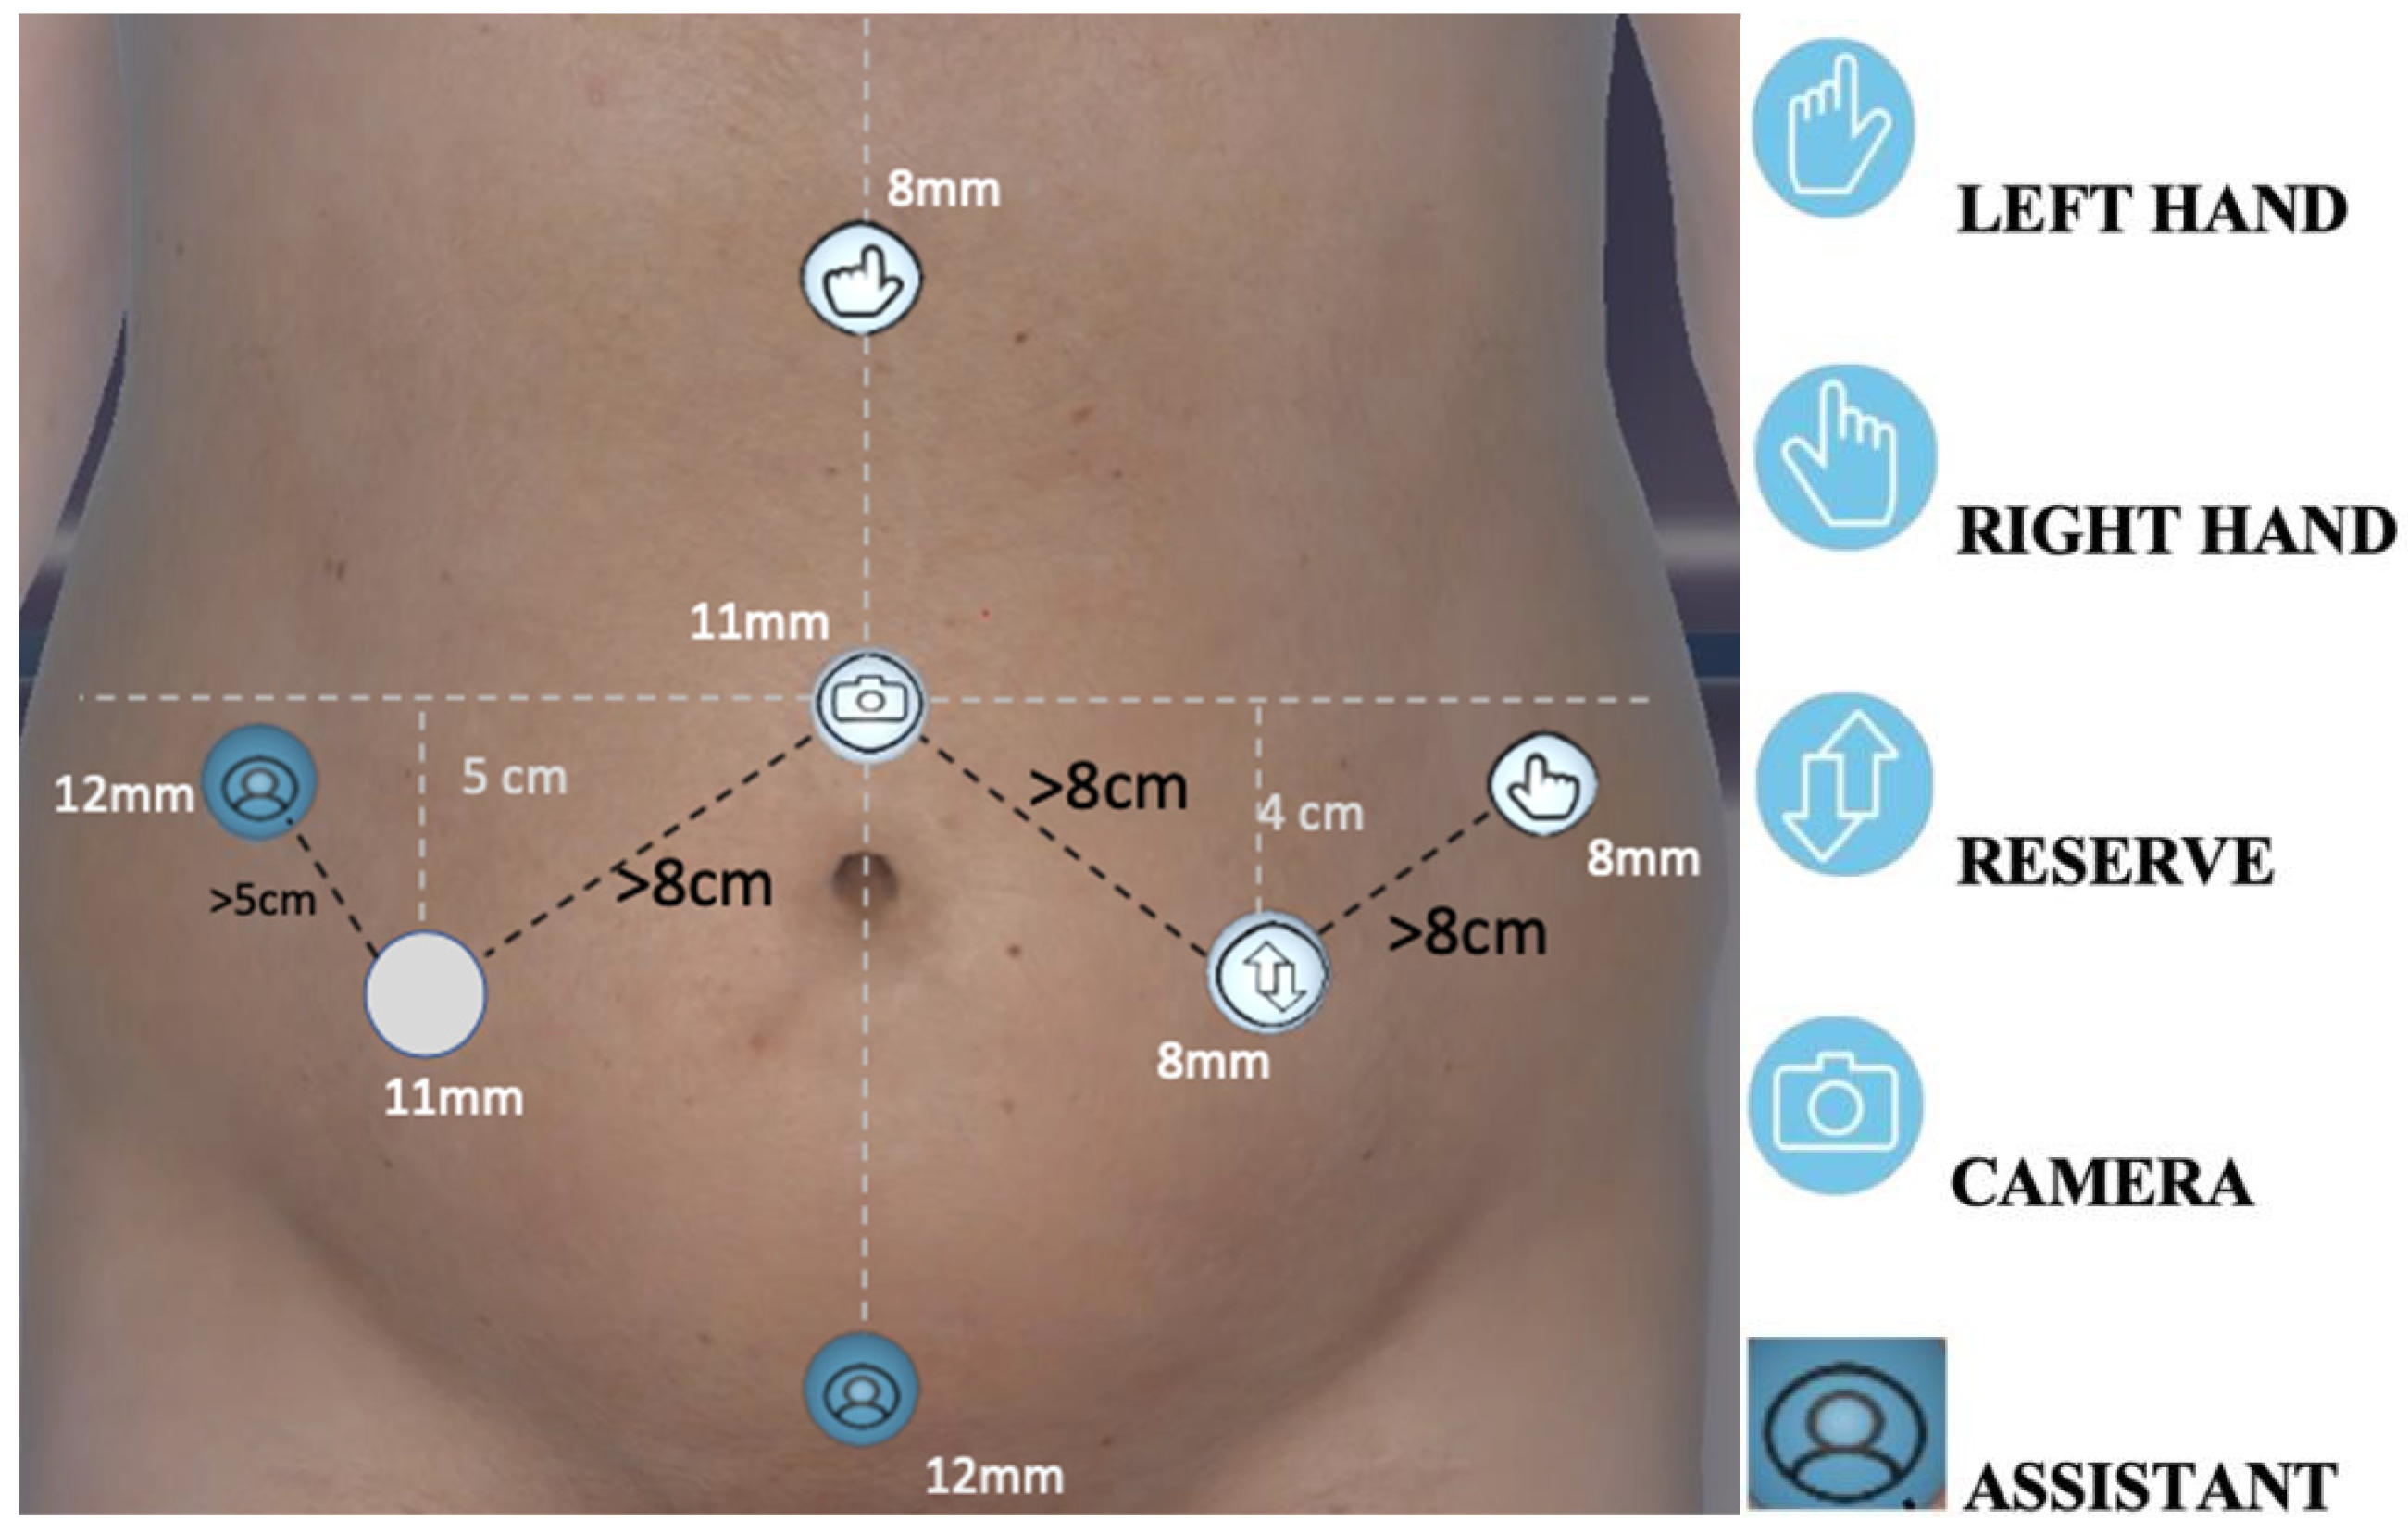
- Right hemicolectomy: 5 ports; 11 mm left para-umbilical robotic port; three additional robotic trocars (one 11 mm in the mesogastrium and two 8 mm in the left hypochondrium and hypogastrium); a 12 mm laparoscopic trocar in the left flank. For right-sided resections, anastomoses were performed intracorporeally using a laparoscopic linear stapler introduced through the 12 mm assistant port. The Pfannenstiel incision was used exclusively for specimen extraction, not for extracorporeal anastomosis (Figure 2).
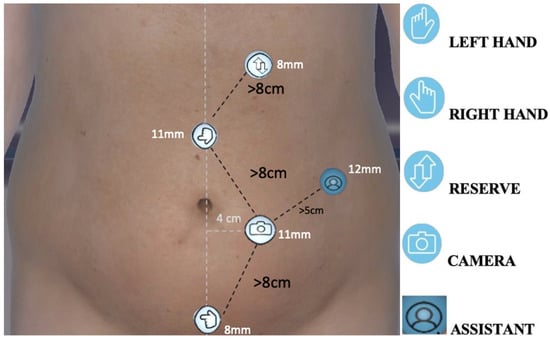
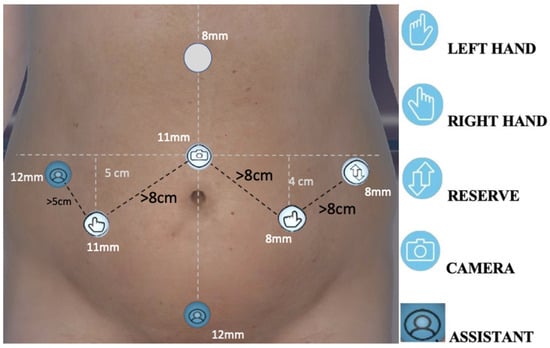
- Left hemicolectomy and sigmoidectomy: 6 ports; 11 mm supra-umbilical robotic port; three 8 mm robotic trocars (epigastric region, left pararectal, left flank); two 12 mm laparoscopic assistant ports (suprapubic region and right flank) (Figure 3).
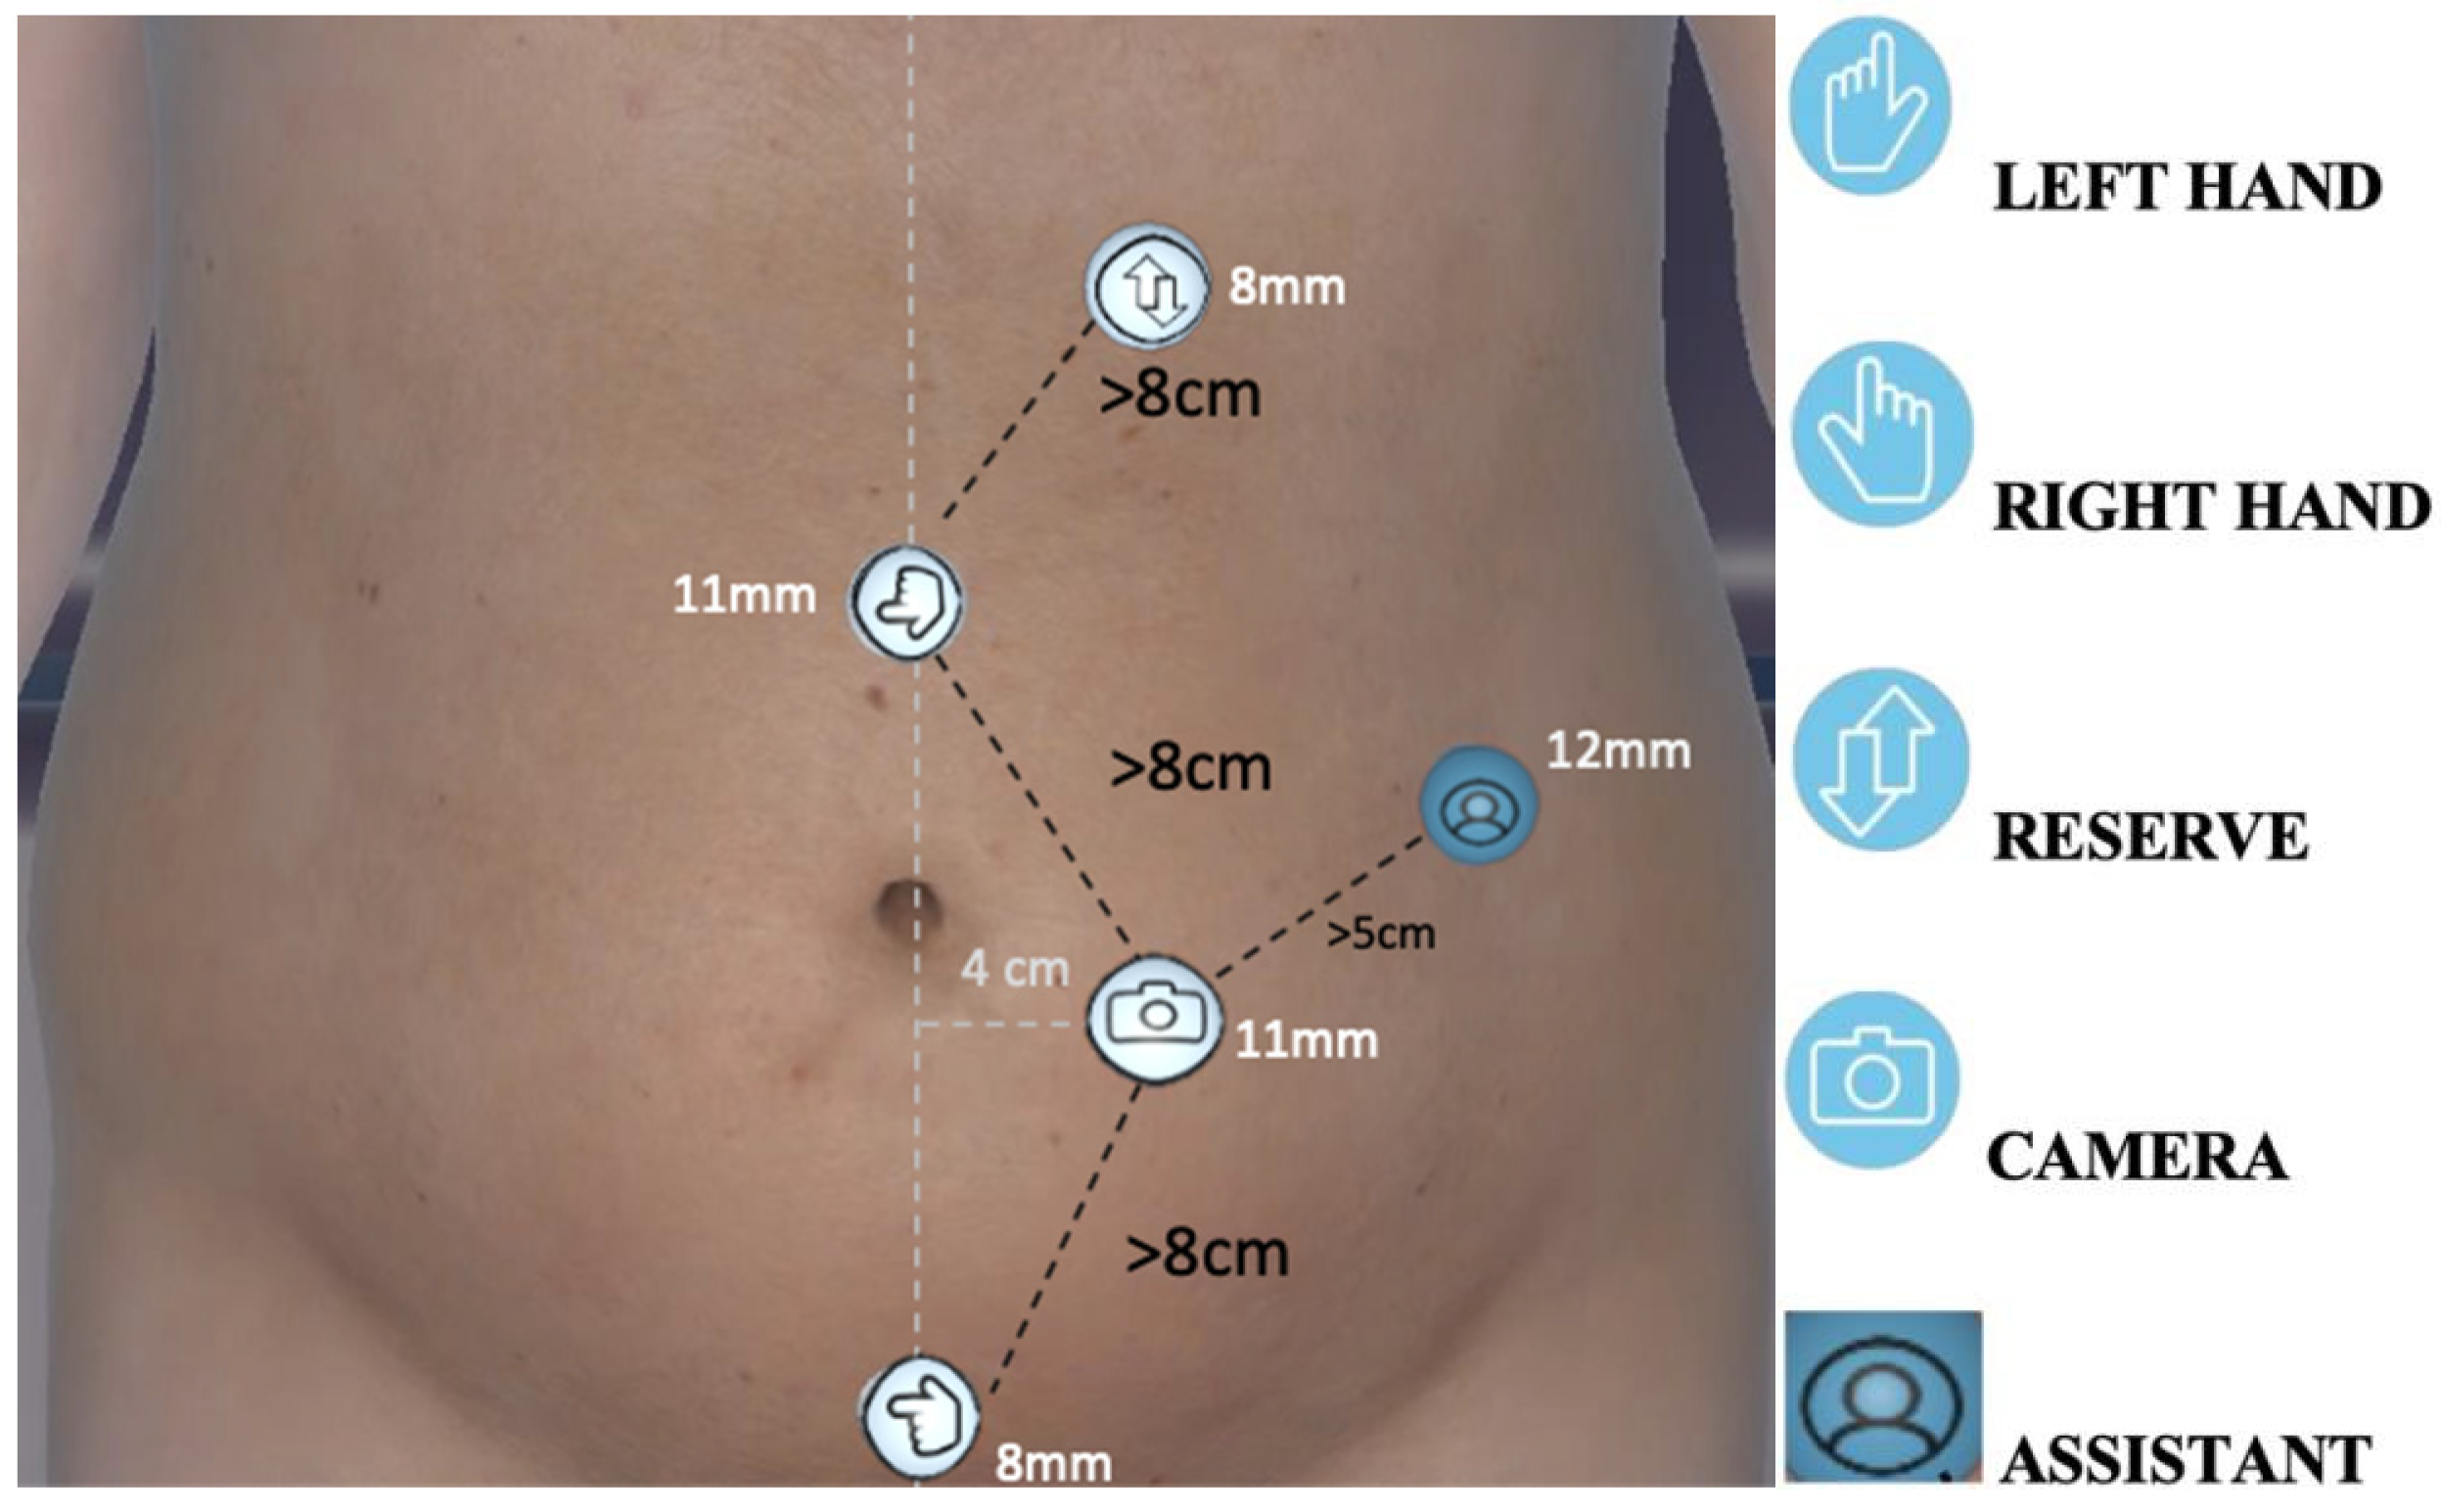
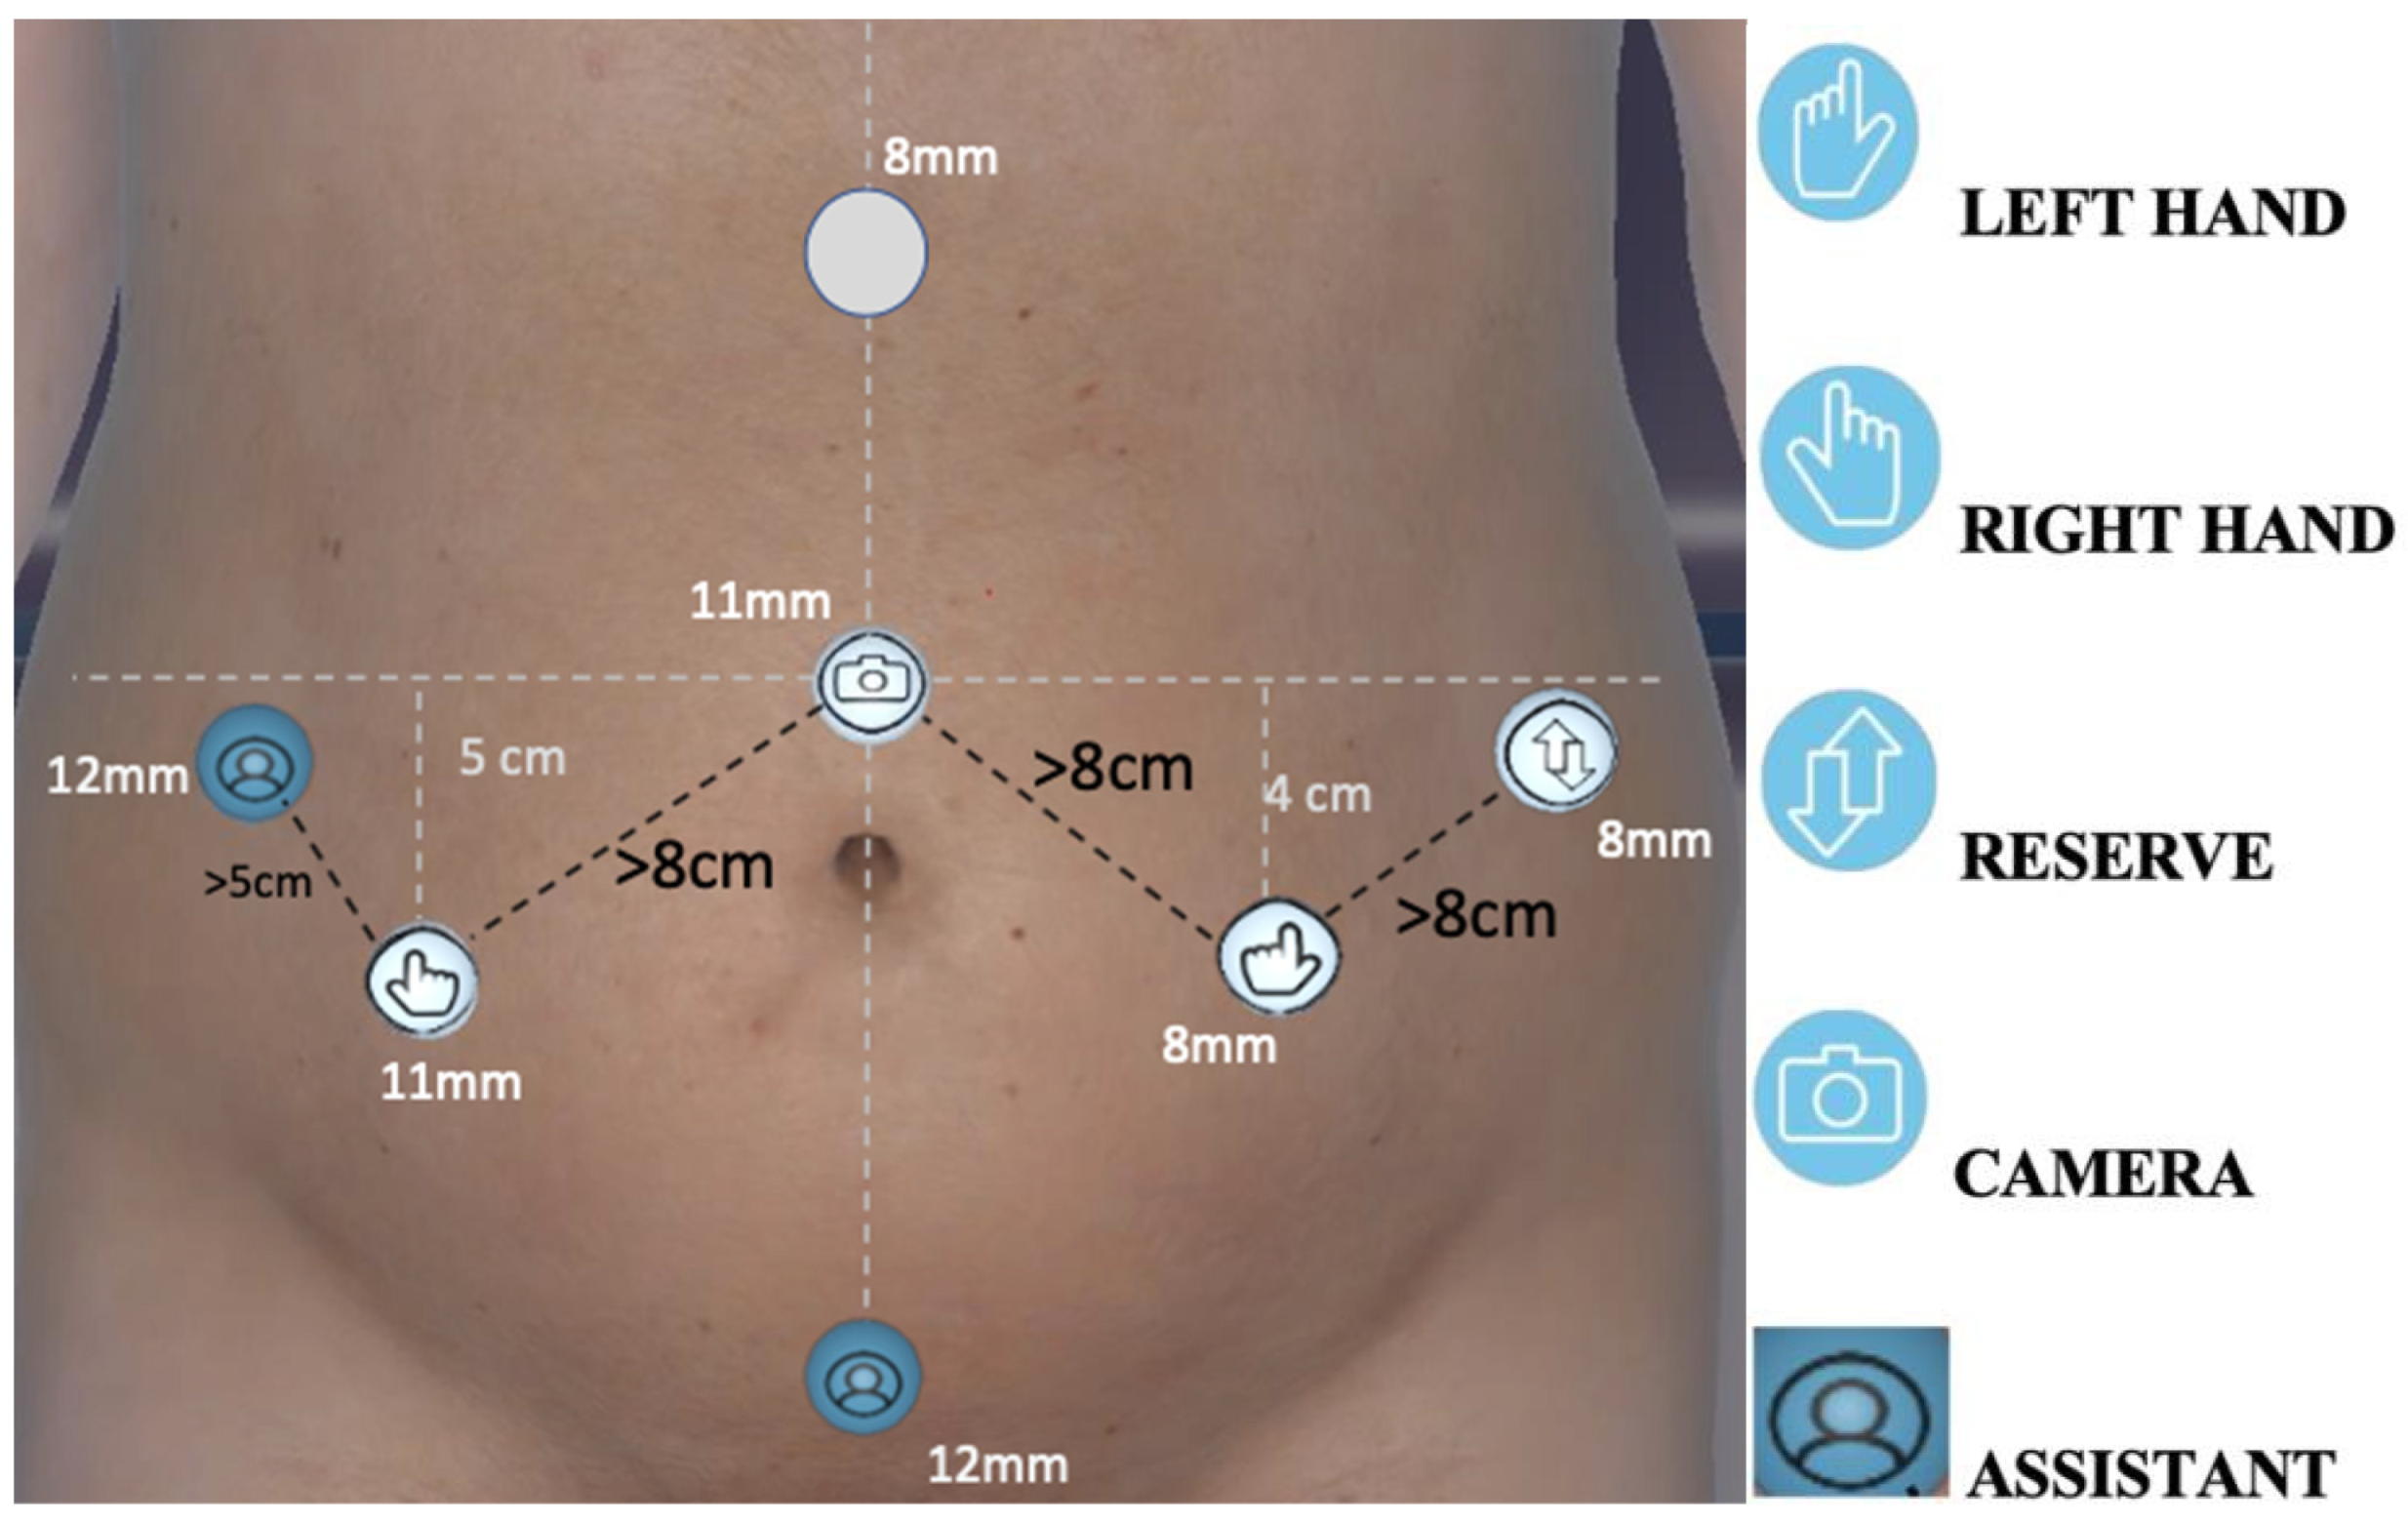
- Anterior rectal resection: 6 ports; 11 mm supra-umbilical robotic port; four additional robotic ports (two 8 mm in left hypogastric region and left flank, one in the epigastric region, one 11 mm in right pararectal hypogastric area); an accessory 12 mm laparoscopic port in the suprapubic region (Figure 4).
Figure 1.
Port placement for splenic flexure resection (without trocars in the right part of the abdomen).
Figure 2.
Port placement for right hemicolectomy.
Figure 3.
Port placement for left hemicolectomy and sigmoidectomy.
Figure 4.
Port placement for anterior rectal resection.
In all procedures, pneumoperitoneum was established via a Veress needle inserted at Palmer’s point, and specimens were extracted through a suprapubic service laparotomy. Postoperative complications were classified according to the Philippe Clavien–Dindo grading system [10]. All patients had a minimum postoperative follow-up period of three months. As part of our institutional follow-up, all patients underwent restaging thoraco-abdominal CT scan at one month after surgery (or earlier if clinically indicated). The primary outcome was to evaluate major colorectal surgical procedures performed with the Hugo RAS system, focusing on perioperative outcomes. Specifically, the analysis included operative time, intraoperative complications, postoperative outcomes within 30 days, and technical aspects including docking configuration and tilt angles. Prior to starting the robotic program, the surgical team completed a simulation-based training course in January 2024. Subsequently, in April 2024, two console surgeons, one bedside assistant and one scrub nurse participated in cadaveric dissection workshops at the ORSI Academy (Ghent, Belgium). All procedures were performed by the same surgical team of colorectal surgeons with extensive minimally invasive surgery experience, though they were at their initial experience with robotic-assisted colorectal procedures.
We obtained the ethical statement approval on 21 December 2022 from Fondazione Policlinico Universitario Campus Bio-Medico di Roma Committee (number: SC 2022.171).
2.1. Statistical Analysis
Statistical analysis was carried out using StataCorp 2019 STATA Statistical Software: release 16 (College Station, TX, USA: StataCorp LLC) and R version 4.1.2 (1 November 2021), (R Foundation for Statistical Computing, Vienna, Austria) by two blinded authors (GC and FC). Descriptive dichotomous data and counts were presented in frequencies, whereas continuous data were presented as mean values ± standard deviations (SD) and/or median and minimum-maximum range.
2.2. Learning Curve Explanation
All surgeons completed simulation training and cadaveric courses (ORSI Academy). The manuscript includes a descriptive learning curve figure showing docking and console time reduction. Due to the small sample size, the learning curve findings are described but not used for inferential analysis, as recommended.
3. Results
A total of 44 patients underwent major colorectal resections using the Hugo™ RAS platform. Patient and disease characteristics are summarized in Table 1. All procedures were completed fully robotically without intraoperative complications or system malfunctions.
Table 1.
Patient and disease characteristics.
The median docking time was 12 min (range 5–20), the median console time was 179 min (range 70–320), and the median total operative time was 308 min (range 200–550). A progressive reduction in both docking and console time was observed after the first 15 cases, indicating a rapid team learning curve. The median redocking time was 5 min (range 2–15), performed mainly for anterior rectal resections requiring additional pelvic readjustment.
The median intraoperative blood loss was 75 mL (range 0–200). No conversions to laparoscopy or laparotomy occurred, and all specimens were extracted through a suprapubic incision. Anastomotic integrity was confirmed intraoperatively in all cases.
The median postoperative hospital stay was 5 days (range 3–13). Fifteen patients (34.1%) experienced postoperative complications, the majority of which were minor (Clavien–Dindo I–II). Major complications (IIIa) occurred in two patients (4.5%), both consisting of anastomotic dehiscence managed successfully with endoscopic vacuum therapy (Endo-SPONGE®), Table 2.
Table 2.
Intraoperative and procedural data. Docking time: from anesthesia clearance to completion of arm deployment; Console time: from surgeon activation of robotic controls to undocking; Total operative time: skin incision to wound closure; Redocking time: time required for repositioning the arm-carts.
No 30-day mortality was observed. Pathological outcomes confirmed negative resection margins and adequate lymph node harvest in all oncologic cases. Overall, the results demonstrate that the Hugo™ RAS platform can safely support the entire spectrum of colorectal resections, from right hemicolectomy to ultra-low anterior resection, during the early adoption phase (Table 3).
Table 3.
Postoperative outcomes.
4. Discussion
This study presents one of the largest single-center experiences to date on the use of the Hugo™ Robotic-Assisted Surgery (RAS) system for major colorectal procedures. Our series of 44 consecutive cases demonstrates that the platform is safe, feasible, and capable of supporting complex colorectal resections without intraoperative complications or conversions to laparoscopy or open surgery. These results confirm the promising early outcomes already reported in smaller preliminary series and highlight the potential of this new robotic platform in the context of minimally invasive colorectal surgery.
From a clinical perspective, this study contributes to expanding the real-world evidence on Hugo™ RAS performance, complementing previous experiences mainly limited to right colectomies or simple segmental resections. The inclusion of rectal procedures in our cohort confirms that the system can safely manage technically demanding operations such as total mesorectal excision.
The global expansion of robotic surgery has been driven by the clear advantages it offers compared with standard laparoscopy, particularly in technically demanding procedures such as total mesorectal excision (TME) and pelvic dissections. The enhanced dexterity of wristed instruments, stable three-dimensional visualization, tremor filtration, and improved ergonomics allow precise dissection in narrow spaces, minimizing fatigue and improving surgeon comfort. However, despite these advantages, robotic surgery has remained limited by high costs and the monopoly of a single manufacturer for nearly two decades [11]. The introduction of the Hugo™ RAS platform represents an important technological and economic turning point, offering a modular, open-console alternative that may increase market competition and, consequently, accessibility [12,13,14].
In our experience, the modular design and independent arm-carts improved positioning flexibility and reduced clashing, particularly during multi-quadrant surgery. These features were especially advantageous in left-sided resections and anterior rectal resections, allowing the surgeon to optimize angles and reach deep pelvic targets without repositioning the system. Over time, docking times decreased significantly, reflecting a short learning curve and efficient team coordination. This finding suggests that dedicated preclinical training and standardized port mapping are key to accelerating proficiency [15,16].
Despite its strengths, some technological limitations of the Hugo™ RAS system must still be acknowledged. Currently, the absence of an integrated robotic stapling device and ICG camera necessitates the use of conventional laparoscopic tools through an assistant port. This requires a highly experienced bedside assistant to ensure workflow efficiency during transection, stapling, or suction maneuvers. Moreover, the system’s current instrument portfolio remains narrower than that of more established platforms, potentially limiting its versatility in certain procedures. Ongoing developments by the manufacturer are expected to address these issues in future updates.
Looking forward, the modular structure and compact footprint of the Hugo™ RAS platform may open new possibilities for hybrid or multi-specialty applications, including urologic and gynecologic collaborations, transanal robotic procedures, and single-docking techniques for multi-quadrant operations. Moreover, integration with digital data platforms and artificial-intelligence–based video analytics could enhance surgical training, ergonomics, and intraoperative safety. These innovations could establish the basis for an advanced ecosystem of “connected” robotic surgery within colorectal practice.
The postoperative outcomes observed in our study align with those reported in the literature for robotic and laparoscopic colorectal surgery [17]. Two patients (4.5%) developed major complications, both consisting of anastomotic leakage in ultra-low colorectal anastomoses. These rates are comparable to those reported in large laparoscopic and robotic TME series, confirming that the risk profile is mainly related to the anatomical and biological complexity of the anastomosis rather than the surgical platform used. The remaining complications were minor (Clavien–Dindo I–II) and self-limiting, reflecting overall safety of the system.
Beyond technical and clinical considerations, the introduction of a new robotic platform also carries institutional and economic implications. Cost containment remains a major barrier to widespread robotic adoption. The Hugo™ RAS system, with its modular architecture and open console design, aims to reduce both acquisition and maintenance costs compared with existing systems [18,19]. A formal cost-effectiveness evaluation will be essential in future studies to verify whether the anticipated economic benefits translate into tangible institutional advantages, particularly in high-volume colorectal units [20].
Compared with established platforms such as the da Vinci® system, Hugo™ RAS offers an open-console design, independent arm-carts, and pistol-grip controllers, potentially improving ergonomics and intraoperative communication. In contrast to Versius®, which uses wristed instruments with bedside units, Hugo™ RAS provides multi-quadrant reach with a four-cart configuration. Cost structures also differ, with Hugo™ RAS designed to reduce capital and maintenance expenses to increase accessibility in mid-volume centers.
This study has some limitations. It represents a single-center experience with a relatively limited sample size, and the follow-up period is too short to draw conclusions about long-term oncologic or functional outcomes. In addition, since all operations were performed by surgeons already experienced in advanced laparoscopy, our results may not fully reflect the initial learning curve of less experienced teams. Nonetheless, the reproducibility and safety observed across different procedures, ranging from right hemicolectomy to ultra-low anterior resection, confirm the versatility of the system and its suitability for a wide range of colorectal indications.
5. Conclusions
Our experience supports the feasibility, safety, and reproducibility of major colorectal resections using the Hugo™ RAS platform. The system offers several technical and ergonomic advantages that may facilitate complex minimally invasive surgery, particularly in the pelvis.
These results confirm that the Hugo™ RAS platform can deliver perioperative outcomes comparable to those of established robotic systems, even during the learning phase, with zero conversions and low morbidity. The rapid reduction in docking time highlights the system’s intuitive configuration and team adaptability.
Beyond demonstrating early safety, this study reinforces the concept that new robotic architectures can expand surgical options while maintaining high standards of precision and patient outcomes. The data also underline the importance of structured training and team standardization to ensure consistent performance.
Future research should include prospective multicenter trials comparing the Hugo™ RAS platform with other robotic systems, focusing on long-term oncologic outcomes, cost analysis, and surgeon learning curves. The potential for broader accessibility and modular integration positions this technology as a promising step toward democratizing robotic colorectal surgery worldwide.
Author Contributions
Conceptualization, F.C. (Filippo Carannante), G.C. and G.T.C.; Data curation, F.C. (Filippo Carannante), P.E.P. and G.T.C.; Formal analysis, F.C. (Filippo Carannante) and G.C.; Investigation, M.M., F.C. (Francesca Carnevale), G.B., V.S. and V.M.; Methodology, F.C. (Filippo Carannante), V.M. and G.C.; Project administration, M.C.; Resources, P.E.P. and V.S.; Software and G.C.; Supervision, M.C.; Validation, F.C. (Filippo Carannante), G.C. and G.T.C.; Visualization, M.C.; Writing—original draft, F.C. (Filippo Carannante) and V.M.; Writing—review and editing, G.C., M.C. and G.T.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declara-tion of Helsinki and approved by the Ethics Committee of Fondazione Policlinico Campus Bio-Medico University of Rome (protocol code number: SC 2022.171).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The data presented in this study are available on request from the corresponding author.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| RAS | Robotic-Assisted Surgery |
| TME | Total Mesorectal Excision |
| CT | Computer tomography |
| AJCC | American Joint Committee on Cancer |
References
- Benson, A.B.; Venook, A.P.; Adam, M.; Chang, G.; Chen, Y.-J.; Ciombor, K.K.; Cohen, S.A.; Cooper, H.S.; Deming, D.; Garrido-Laguna, I.; et al. Colon Cancer, Version 3.2024, NCCN Clinical Practice Guidelines in Oncology. J. Natl. Compr. Cancer Netw. 2024, 22, e240029. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vogel, J.D.; Felder Seth, I.; Bhama Anuradha, R.; Hawkins Alexander, T.; Langenfeld Sean, J.; Shaffer Virginia, O.; Thorsen Amy, J.; Weiser Martin, R.; Chang George, J.; Lightner Amy, L.; et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Colon Cancer. Dis. Colon Rectum 2022, 65, 148–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghadimi, M.; Rödel, C.; Hofheinz, R.; Flebbe, H.; Grade, M. Multimodal Treatment of Rectal Cancer. Dtsch. Arztebl. Int. 2022, 119, 570–580. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, S.W.; Crowe, P. Visualisation ergonomics and robotic surgery. J. Robot. Surg. 2023, 17, 1873–1878. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Belyaev, O.; Fahlbusch, T.; Slobodkin, I.; Uhl, W. Major colorectal surgery with Hugo™ RAS: Initial experience of a German center and a review of the literature. Updates Surg. 2024; in press. [CrossRef] [Scilit] [PubMed]
- Marchegiani, F.; Siragusa, L.; Zadoroznyj, A.; Laterza, V.; Mangana, O.; Schena, C.A.; Ammendola, M.; Memeo, R.; Bianchi, P.P.; Spinoglio, G.; et al. New Robotic Platforms in General Surgery: What’s the Current Clinical Scenario? Medicina 2023, 59, 1264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prata, F.; Ragusa, A.; Tempesta, C.; Iannuzzi, A.; Tedesco, F.; Cacciatore, L.; Raso, G.; Civitella, A.; Tuzzolo, P.; Callè, P.; et al. State of the Art in Robotic Surgery with Hugo RAS System: Feasibility, Safety and Clinical Applications. J. Pers. Med. 2023, 13, 1233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bianchi, P.P.; Salaj, A.; Rocco, B.; Formisano, G. First worldwide report on Hugo RAS™ surgical platform in right and left colectomy. Updates Surg. 2023, 75, 775–780. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amin, M.B.; Greene, F.L.; Edge, S.B.; Compton, C.C.; Gershenwald, J.E.; Brookland, R.K.; Meyer, L.; Gress, D.M.; Byrd, D.R.; Winchester, D.P. The Eighth Edition AJCC Cancer Staging Manual: Continuing to build a bridge from a population-based to a more “personalized” approach to cancer staging. CA Cancer J. Clin. 2017, 67, 93–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dindo, D.; Demartines, N.; Clavien, P.A. Classification of surgical complications: A new proposal with evaluation in a cohort of 6336 patients and results of a survey. Ann. Surg. 2004, 240, 205–213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gangemi, A.; Bernante, P.; Rottoli, M.; Pasquali, F.; Poggioli, G. Surgery of the alimentary tract for benign and malignant disease with the novel robotic platform HUGOTM RAS. A first world report of safety and feasibility. Int. J. Med. Robot. Comput. Assist. Surg. 2023, 19, e2544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Romero-Marcos, J.M.; Sampson-Davila, J.G.; Cuenca-Gomez, C.; Altet-Torne, J.; Gonzalez-Abos, S.; Ojeda-Jimenez, I.; Galaviz-Sosa, M.L.; Delgado-Rivilla, S. Colorectal procedures with the novel HugoTM RAS system: Training process and case series report from a non-robotic surgical team. Surg. Endosc. 2024, 38, 2160–2168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rottoli, M.; Cardelli, S.; Calini, G.; Alexa, I.D.; Violante, T.; Poggioli, G. Outcomes of robotic surgery for inflammatory bowel disease using the Medtronic Hugo™ Robotic-Assisted Surgical platform: A single center experience. Int. J. Color. Dis. 2024, 39, 158. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arroyo, A.; Sánchez-Romero, A.; Soler-Silva, Á.; Quinto, S.; López-Rodríguez-Arias, F.; Alcaide, M.J.; Serrano-Navidad, M.; Miranda, E.; Muñoz, J.L.; Sánchez-Guillén, L. Utility guideline and considerations for the novel Hugo™ RAS (robotic-assisted surgery) system in colorectal surgery: Surgical outcomes and initial experience in a tertiary center. Int. J. Color. Dis. 2024, 39, 144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rottoli, M.; Violante, T.; Calini, G.; Cardelli, S.; Novelli, M.; Poggioli, G. A multi-docking strategy for robotic LAR and deep pelvic surgery with the Hugo RAS system: Experience from a tertiary referral center. Int. J. Color. Dis. 2024, 39, 154. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Violante, T.; Rottoli, M.; Colpaert, J.; Poortmans, M.; Boterbergh, K.; Potvlieghe, P.; Van Campenhout, I. A right colectomy case study: Transitioning to the Hugo RAS system with a novel 3-ports technique in experienced robotic colorectal practice. Langenbeck’s Arch. Surg. 2024, 409, 368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Calini, G.; Cardelli, S.; Alexa, I.D.; Andreotti, F.; Giorgini, M.; Greco, N.M.; Agama, F.; Gori, A.; Cuicchi, D.; Poggioli, G.; et al. Colorectal Cancer Outcomes of Robotic Surgery Using the Hugo™ RAS System: The First Worldwide Comparative Study of Robotic Surgery and Laparoscopy. Cancers 2025, 17, 1164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carannante, F.; Miacci, V.; Piozzi, G.N.; Marrelli, M.; Caricato, M.; Khan, J.S.; Capolupo, G.T. Splenic flexure resection with Hugo™ RAS: Trocar placement, docking settings, and surgical strategy. Color. Dis. 2025, 27, e70242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boggi, U.; Vistoli, F.; Amorese, G. Twenty years of robotic surgery: A challenge for human limits. Updates Surg. 2021, 73, 789–793. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sighinolfi, M.C.; Messina, L.A.; Stocco, M.; Moscovas, M.C.; Pelliccia, P.; Palma, A.; Rossini, M.; Gallo, A.; Ramondo, A.; Pozzi, E.; et al. Cost analysis of new robotic competitors: A comparison of direct costs for initial hospital stay between Da Vinci and Hugo RAS for radical prostatectomy. J. Robot. Surg. 2024, 18, 251. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).