Skip to Content
You are currently on the new version of our website. Access the old version .
  • Tracked for
    Impact Factor
  • 4.2
    CiteScore
  • 51 days
    Submission to First Decision
  • 6 days
    Acceptance to Publication

Gout, Urate, and Crystal Deposition Disease

Gout, Urate, and Crystal Deposition Disease (GUCDD) is an international, peer-reviewed, open access journal on gout, urate, and crystal deposition disease, published quarterly online. It is the official journal of the Gout, Hyperuricemia and Crystal Associated Disease Network (G-CAN). Network members receive discounts on the article processing charges.
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions. If you become a member of G-CAN you will benefit of 20% discount on the APC.
  • High Visibility: indexed within ESCI (Web of Science), Scopus and other databases.
  • Journal Rank: CiteScore - Q2 (Medicine (miscellaneous))
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 50.6 days after submission; acceptance to publication is undertaken in 5.7 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (86)

  • Review
  • Open Access

GLP-1 Receptor Agonists and Gout: A Narrative Review

  • Charlie Flint,
  • Tony R. Merriman and
  • Daniel H. Solomon

Glucagon-like peptide-1 receptor agonists (GLP-1 RAs) and glucose-dependent insulinotropic polypeptide receptor agonists (GIP RAs) are incretin mimetics that have increased in use in the management of type 2 diabetes and obesity. Understanding the potential impact of incretin mimetics on gout is important because of their increased use and the relationship between obesity, insulin resistance, hyperuricemia, and gout. Current evidence supports that both metabolic and inflammatory pathways overlap between incretin mimetics and gout. Some data suggest a biphasic effect of GLP-1 RAs on gout risk—initially increasing gout flare risk and eventually decreasing flare risk, but this needs confirmation in larger prospective studies. The rapid weight loss that is seen on incretin mimetics may alter the renal handling of uric acid due to the presence of ketone bodies. However, sustained weight reduction and the direct inhibition of NF-κB signaling, reduced NLRP3 inflammasome activation, and alterations in macrophage polarization may reduce gout-related inflammation over the longer term. This narrative review aims to summarize the current understanding of the pharmacologic, metabolic, and immunologic mechanisms linking incretin mimetics with gout and aims to explore the potential implications for clinical management of gout.

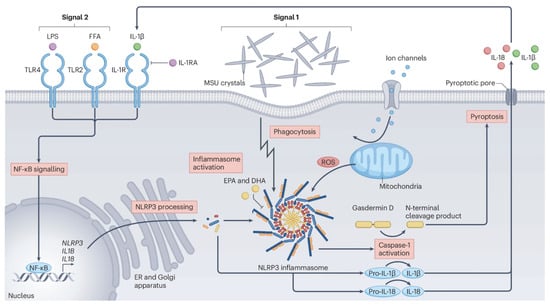
Illustration of gout physiology and the two-signal pathway occurring from monosodium crystals. Two signals are required to activate the NLRP3 inflammasome. The inflammatory response is primed by TLR receptor activation which turns on NFkB pathways. NFkB mediates the transcription of NLRP3, pro-IL-1β, and pro-IL-18. The activation of NLRP3 is initiated by the phagocytosis of MSU crystals, and the NLRP3 inflammasome is assembled. Caspase-1 is also activated, and cleaves gasdermin D, pro-IL-1β, and pro-IL-1β into their active forms. Gasdermin D facilitates pyroptosis and the subsequent cytokine storm. (Adapted with permission from Nature Reviews Rheumatology [7]).
  • Review
  • Open Access

Gout in North America

  • Divya Sudireddy,
  • Madeeha Shaikh and
  • Timothy S. H. Kwok
  • + 3 authors

Gout is the most prevalent inflammatory arthritis in North America, affecting approximately 3.8% of the population in Canada and 5.1% in the United States (US). Epidemiological modeling through 2050 projects that high-income North America will sustain the highest age-standardized prevalence of gout globally. This rising burden is accompanied by heavy socioeconomic costs and striking demographic shifts. Driven by obesity, early-onset gout among American youth escalated by 63% over the last three decades, while nearly one-third of US adolescents now exhibit hyperuricemia, in contrast to ~20% of adults. Furthermore, profound racial inequities persist; Black patients experience a five-fold higher rate of emergency department (ED) visits for gout flares compared to White patients, and older Asian Americans face the highest overall prevalence. Primary care providers manage 70% to 80% of gout cases in both nations. Suboptimal longitudinal care has led to severe reliance on acute services. Post-ED care continuity remains poor, frequently resulting in low rates of follow-up serum urate testing, high readmission rates, and inappropriate opioid prescribing. Diagnostically, polarizing light microscopy of synovial fluid remains the gold standard, supplemented by advanced ultrasound and dual-energy computed tomography imaging, although this technology is limited by provider availability. Treatment paradigms prioritize a treat-to-target strategy to maintain serum urate levels below 6 mg/dL. Allopurinol is the preferred first-line therapy, with recent clinical data validating its safety and efficacy when progressively titrated in patients with chronic kidney disease. Second-line febuxostat requires shared decision making in the context of cardiovascular disease, while advanced, refractory tophaceous gout is managed in the US with intravenous pegloticase which can be co-administered with methotrexate to mitigate immunogenicity. Ultimately, optimizing North American gout outcomes requires improvement in health services delivery with multidisciplinary models of care serving as an emerging solution.

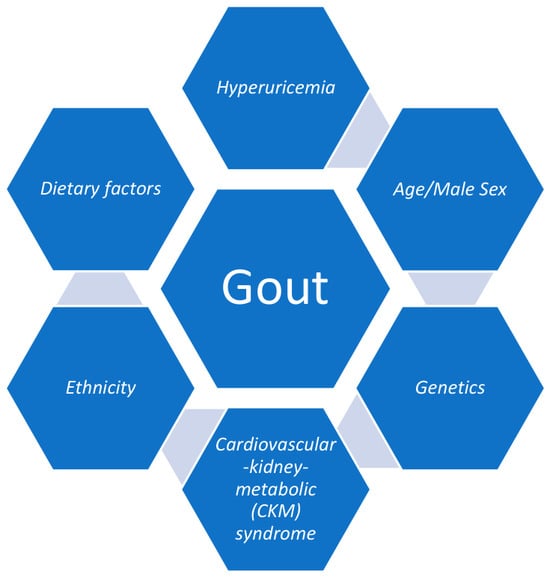
Selected gout risk factors in North America.
  • Article
  • Open Access

Background and Objectives: The nomenclature of calcium pyrophosphate deposition (CPPD) disease remains confusing, with different labels used interchangeably to describe the disease. Although ‘CPPD disease’ is the term that has been recommended by EULAR since 2011, ‘pseudogout’ remains the most frequently used label in the medical literature. This study aimed to investigate how the labels ‘CPPD disease’ versus ‘pseudogout’ affect the public’s perceptions of the illness. Methods: In this randomized controlled single-blind study, 200 members of the public watched a 2 min video describing a form of arthritis labeled as either ‘CPPD disease’ or ‘pseudogout’. Participants then completed a questionnaire assessing their perceptions of the illness using the Brief Illness Perception Questionnaire (BIPQ), with additional questions about their perceived seriousness of the illness and embarrassment associated with it, and beliefs about causes and management strategies. The primary outcome was the level of embarrassment associated with the illness. Results: Overall, embarrassment scores were low with no significant difference between the ‘CPPD disease’ and ‘pseudogout’ groups. Participants in both groups viewed the illness as being serious. There were no differences between the groups in their responses to the BIPQ, nor in their beliefs on the likely causes and management strategies. Even after a video intervention, participants’ understanding of the illness remained low. Conclusions: The labels ‘CPPD disease’ and ‘pseudogout’ do not differentially influence perceptions about the illness among members of the public. This could be due to the lack of knowledge about CPPD disease, highlighting the need to increase public awareness of this important condition.

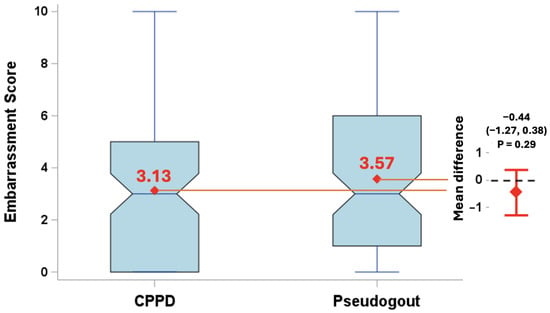
Perceived level of embarrassment associated with a diagnosis of the condition according to whether a participant watched the video on ‘CPPD disease’ or the video on ‘pseudogout’. Scale 0–10, with 0 indicating “not at all embarrassed” and 10 indicating “extremely embarrassed”.
  • Review
  • Open Access

Humans and other great apes are unique among animals in lacking functional uricase, an enzyme that breaks down urate and allows its excretion. Modern-day humans have elevated serum urate, which is associated with various chronic health issues, including gout, metabolic syndrome, and hypertension. This prompts the question: what is the evolutionary benefit of the loss of uricase function, given that it may confer an increased risk of these chronic diseases? In this review, we explore numerous possible advantages, including some less commonly discussed, such as urate’s function as an antioxidant, its roles in ancestral survival, and its metabolic role in the context of our evolutionary history and the environmental pressures that have shaped human biology. We go on to examine the tradeoffs of urate’s evolutionary advantages, and how these features may be a double-edged sword for our health in our modern environment characterized by a caloric abundance of key nutrients, such as fructose, which are intimately linked with urate production and/or metabolism. Moving forward, we suggest that future work should explore the role of our evolutionary history in the rising prevalence of gout and other modern-day metabolic diseases. We further recommend that drugs and therapeutic strategies for diseases such as gout be informed by an understanding of the rich evolutionary context from which these maladies emerged and the unifying role of serum urate across these disease states.

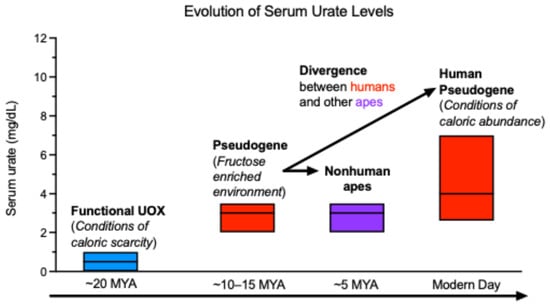
Theoretical changes in serum urate with changes in UOX function and food supply across an evolutionary timescale.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Gout Urate Cryst. Depos. Dis. - ISSN 2813-4583