-
Knowledge, Attitudes, and Perceptions of Midwives and Obstetricians/Gynecologists on Sexual Activity During Pregnancy: A Cross-Sectional Study in Greece -
Myoprotective Fat-Loss Phenotypes in Obesity-Associated Type 2 Diabetes: A 12-Month Real-World Cohort Study of Metformin-Based Treatment Regimens -
Revision After Total Ankle Arthroplasty: A Cross-Registry Analysis
Journal Description
Clinics and Practice
is an international, peer-reviewed, open access journal on clinical medicine, published monthly online by MDPI (from Volume 11, Issue 1 - 2021).
- Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
- High Visibility: indexed within Scopus, ESCI (Web of Science), PubMed, PMC, Embase, and other databases.
- Journal Rank: JCR - Q1 (Medicine, General and Internal) / CiteScore - Q1 (General Medicine)
- Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 24 days after submission; acceptance to publication is undertaken in 2.8 days (median values for papers published in this journal in the first half of 2026).
- Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.
- Journal Clusters of Surgery: Journal of Clinical Medicine, Surgical Techniques Development, Reports — Clinical Practice and Surgical Cases, Surgeries, Clinics and Practice, European Burn Journal, Complications, Osteology, Transplantology, Anesthesia Research, Emergency Care and Medicine and Journal of Aesthetic Medicine.
Impact Factor:
2.8 (2025);
5-Year Impact Factor:
2.4 (2025)
Latest Articles
Effects of Telenursing on Self-Care and Healthcare Outcomes in Patients with Heart Failure: A Systematic Review
Clin. Pract. 2026, 16(10), 183; https://doi.org/10.3390/clinpract16100183 - 30 Sep 2026
Abstract
Background/Objectives: Heart failure (HF) remains a major public health challenge, requiring continuous management and high patient adherence to prevent exacerbations. Telenursing offers a scalable, tailored solution for remote monitoring and education; however, evidence regarding optimal individualized intervention models remains heterogeneous, necessitating a systematic
[...] Read more.
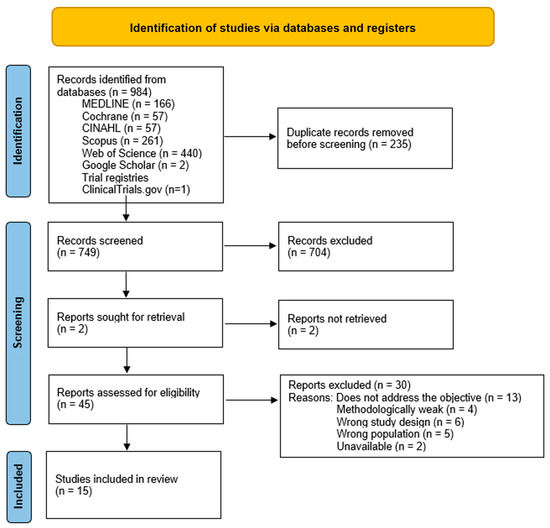
Background/Objectives: Heart failure (HF) remains a major public health challenge, requiring continuous management and high patient adherence to prevent exacerbations. Telenursing offers a scalable, tailored solution for remote monitoring and education; however, evidence regarding optimal individualized intervention models remains heterogeneous, necessitating a systematic synthesis within the framework of precision care. This study aims to identify the effects of telenursing on self-care capacity and health outcomes in patients with heart failure. Methods: A systematic review was conducted following JBI methodology and PRISMA guidelines. Six databases (MEDLINE, Cochrane, CINAHL, Scopus, Web of Science, Google Scholar) were searched for studies (2020–2025). Quality was assessed using JBI Critical Appraisal Tools (threshold > 60%). Results: Fifteen studies were included from the 748 identified. Three core personalized modalities were categorized: tailored self-care digital programs, mobile applications, and integrated telemonitoring systems. Interventions featuring individualized, risk-stratified, and frequent contact demonstrated a significant positive impact on self-care behaviors, NYHA classification, and hospitalization rates. Key components included personalized vital sign alerts, structured virtual interviews, and digital coaching. Nurse-led oversight directly supported clinical responsiveness and medication adherence, though therapeutic efficacy varied according to baseline patient digital literacy and cognitive function. Conclusions: Technology-enabled personalized nursing interventions are highly effective in enhancing self-care skills, health literacy, and clinical stability. Future research should prioritize large-scale trials with prolonged follow-up and cost-effectiveness analyses to support multidisciplinary integration.
Full article
(This article belongs to the Special Issue Digital Health and Virtual Care Innovations: Applications for Long-Term Care and Self-Management Support)
►
Show Figures

Open AccessArticle
Association of Ultrafiltration Rate with Structural Remodeling of the Left Heart and Arrhythmias in Hemodialysis Patients: A Cross-Sectional Observational Study
by
Ammar Brkić, Kenana Ljuca, Emir Tulumović, Nadina Ljuca, Nermin Salkić, Emir Bećirović, Amir Tursunović, Minela Bećirović and Bahrudin Hadžiefendić
Clin. Pract. 2026, 16(10), 182; https://doi.org/10.3390/clinpract16100182 - 30 Sep 2026
Abstract
Background/aim: Hemodialysis patients face a high burden of cardiovascular diseases, which account for over 40% of mortality in this population. In these patients, approximately two-thirds of cardiovascular deaths are due to arrhythmia. The aim of this study was to determine whether the ultrafiltration
[...] Read more.
Background/aim: Hemodialysis patients face a high burden of cardiovascular diseases, which account for over 40% of mortality in this population. In these patients, approximately two-thirds of cardiovascular deaths are due to arrhythmia. The aim of this study was to determine whether the ultrafiltration rate is associated with morphological and functional parameters of the left heart and arrhythmias. Methods: This work was a cross-sectional observational clinical study, with 75 hemodialysis patients. Patients were divided into two groups based on ultrafiltration rate (UFR): higher-UFR group, ultrafiltration rate ≥ 10 mL/kg/h (n = 37); lower-UFR group, ultrafiltration rate < 10 mL/kg/h (n = 38). All patients were analyzed for myocardial morphological and functional parameters and arrhythmias. Results: Statistically significant higher values were observed for the left atrium diameter (LAD) (47.56 ± 4.82 vs. 44.75 ± 2.33 mm, p = 0.0019), the left atrial volume index (LAVI) (43.28 ± 7.13 vs. 36.43 ± 8.52 mL/m2, p = 0.0003), and the left ventricular mass index (LVMI) (138.47 ± 29.32 vs. 116.04 ± 31.64 g/m2, p = 0.0021) in the higher-UFR group. UFR was associated with LAD (OR: 3.6000, 95% CI: 1.3780–9.4053, p = 0.0089), LAVI (OR: 4.1067, 95% CI: 1.5478–10.8956, p = 0.0045), and LVMI (OR: 4.7619, 95% CI: 1.6825–13.4774, p = 0.0033). The frequency of ventricular and supraventricular arrhythmias was similar between the analyzed patient groups. Conclusions: Higher UFR was associated with structural changes in the left heart (LAVI, LAD, and LVMI), but not with other echocardiographic parameters or arrhythmias in hemodialysis patients.
Full article
(This article belongs to the Section Cardiac and Cardiovascular Systems)
Open AccessSystematic Review
AI-Assisted Clinical Decision Support Versus Standard Teleconsultation in Adult Medicine: A Systematic Review of Diagnostic Accuracy, Referral and Testing Decisions, and Clinician Confidence
by
Yaslam Ba Srada, Bobakr Bawazir, Saad Mohammad Aghi, Mohamed Elsayed, Hisham Yousif, Mohamed Ibrahim, Kareem Adel Eltohamy and Mark Sim
Clin. Pract. 2026, 16(10), 181; https://doi.org/10.3390/clinpract16100181 - 30 Sep 2026
Abstract
Background/Objectives: Artificial intelligence (AI) is increasingly integrated into teleconsultation, but its effects on clinician performance remain uncertain. We assessed whether clinician-facing AI improves diagnostic accuracy, reduces referrals or testing, and increases clinician confidence compared with standard teleconsultation or conventional resources. Methods: This retrospectively
[...] Read more.
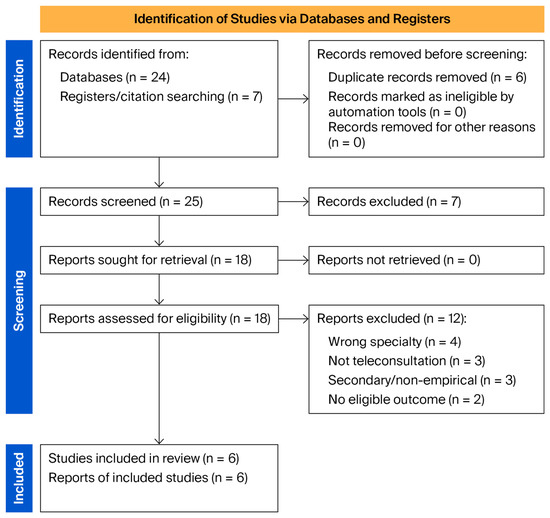
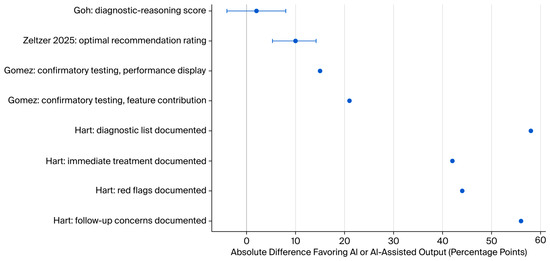
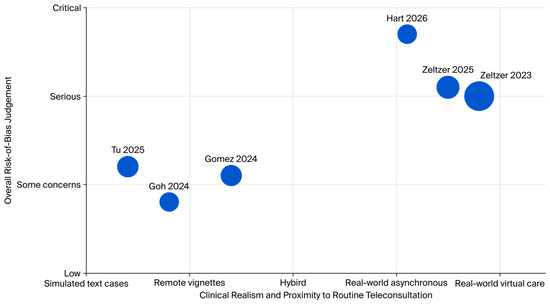
Background/Objectives: Artificial intelligence (AI) is increasingly integrated into teleconsultation, but its effects on clinician performance remain uncertain. We assessed whether clinician-facing AI improves diagnostic accuracy, reduces referrals or testing, and increases clinician confidence compared with standard teleconsultation or conventional resources. Methods: This retrospectively registered systematic review followed the PRISMA 2020 and Synthesis Without Meta-Analysis (SWiM) guidance. PubMed/MEDLINE, publisher-indexed platforms, Google Scholar, ClinicalTrials.gov, and backward and forward citation searches were performed from inception to 1 August 2026. Eligible studies evaluated clinician-facing AI in adult primary, urgent, or general medical teleconsultation or in high-fidelity virtual consultation designs and reported diagnostic, referral/testing, or confidence outcomes. One reviewer screened records, extracted data, and assessed the risk of bias using the design-appropriate QUADAS-2, RoB 2, and ROBINS-I domains, with a second pass for consistency. Owing to clinical and methodological heterogeneity, the results were synthesized narratively. Results: Of 31 records identified, 25 remained after duplicate removal, 18 full texts were assessed, and six studies were included: two randomized virtual experiments, two retrospectives virtual care cohorts, one randomized crossover conversational AI study, and one provider-to-provider telemedicine case series. In a telehealth screening experiment, AI improved diagnostic prediction, but physicians given a large language model showed no significant benefit (adjusted difference, two percentage points; 95% CI, −4 to 8). Across 102,059 virtual encounters, an AI-generated differential included the clinician’s final diagnosis in 84.2%, although the reference was not independent. AI-assisted urgent care recommendations were rated optimal more often than final physician recommendations (77.1% vs. 67.1%). AI did not reduce unnecessary referrals; one experiment found more confirmatory testing requests and lower trust than with a familiar clinical score. Certainty was low or very low for the principal clinical outcomes. Conclusions: AI may support teleconsultation decisions, but evidence that it reduces unnecessary referrals or meaningfully increases clinician confidence is insufficient. Pragmatic trials using independent patient-level reference standards are needed. Registration: This completed review was retrospectively registered on the Open Science Framework (OSF); no protocol was published before study selection.
Full article
(This article belongs to the Topic Artificial Intelligence in Public Health: Current Trends and Future Possibilities, 3rd Edition)
►▼
Show Figures

Figure 1
Open AccessReview
Stroke in Young Adults: A Narrative Review of Clinico-Radiological Approach to Twenty Key Etiologies
by
Bruno Kusznir Vitturi, Felipe Torres Pacheco and Rubens José Gagliardi
Clin. Pract. 2026, 16(10), 180; https://doi.org/10.3390/clinpract16100180 - 29 Sep 2026
Abstract
Background: Stroke in young adults is increasing worldwide and is associated with substantial long-term disability. Unlike stroke in older populations, young patients frequently present with uncommon etiologies that require specific diagnostic approaches and targeted secondary prevention strategies. Early recognition of these causes remains
[...] Read more.
Background: Stroke in young adults is increasing worldwide and is associated with substantial long-term disability. Unlike stroke in older populations, young patients frequently present with uncommon etiologies that require specific diagnostic approaches and targeted secondary prevention strategies. Early recognition of these causes remains a major clinical challenge. Objective: This study aimed to provide a comprehensive review of the principal uncommon causes of stroke in young adults, emphasizing their clinical characteristics and neuroimaging findings relevant to etiological diagnosis. Methods: A narrative review was conducted focusing on cerebrovascular disorders that disproportionately affect young adults, including arterial dissections, patent foramen ovale, moyamoya disease, reversible cerebral vasoconstriction syndrome, cerebral venous thrombosis, thrombophilias, autoimmune diseases, infections, genetic disorders, malignancy, and cardiac conditions. Particular attention was given to neuroradiological patterns and imaging modalities useful for diagnosis. Results: Numerous uncommon etiologies contribute significantly to stroke in young adults and often occur in the absence of traditional vascular risk factors. Neuroimaging plays a pivotal role in diagnosis, helping identify characteristic findings such as double-lumen signs in arterial dissections, collateral vessel networks in moyamoya disease, reversible multifocal vasoconstriction in RCVS, venous filling defects in cerebral venous thrombosis, and distinctive imaging signatures associated with genetic, infectious, inflammatory, and neoplastic disorders. Recognition of these patterns can substantially improve diagnostic accuracy and guide appropriate secondary prevention. Conclusions: Stroke in young adults encompasses a broad spectrum of etiologies that differ considerably from those observed in older populations. Awareness of characteristic clinical and neuroimaging features is essential for accurate etiological investigation and implementation of effective preventive strategies.
Full article
Open AccessArticle
The Relationship Between Interferon Status and HPV Infection in Patients with Oral Epithelial Dysplasia: An Observational Study
by
Guzel Khisamieva, Diana Sologova, Oxana Svitich, Ekaterina Diachkova, Victoria Morozova, Anna Maltseva, Rashid Aliyev and Mikhail Stepanov
Clin. Pract. 2026, 16(10), 179; https://doi.org/10.3390/clinpract16100179 - 28 Sep 2026
Abstract
Background/Objectives: Oral potentially malignant diseases (OPMDs) with signs of epithelial dysplasia are characterized by a high risk of malignancy. However, there are still no algorithms for their early diagnosis and prediction, due to the many possible predisposing factors, including human papillomavirus (HPV)
[...] Read more.
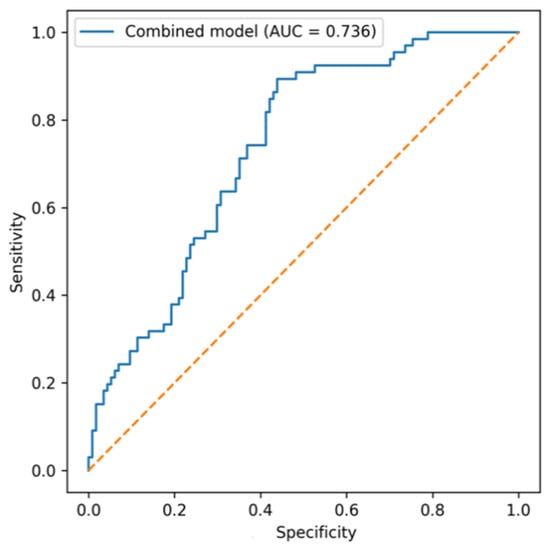
Background/Objectives: Oral potentially malignant diseases (OPMDs) with signs of epithelial dysplasia are characterized by a high risk of malignancy. However, there are still no algorithms for their early diagnosis and prediction, due to the many possible predisposing factors, including human papillomavirus (HPV) infection and decreased immunity. There is a need to assess the relationship between the manifestations of oral epithelial dysplasia (OED), HPV invasion in the oral cavity, and interferon status to improve the identification and characterization of patients with different degrees of dysplasia. Methods: This study was designed and reported with reference to the STROBE checklist. The study aimed to assess the association between interferon status and HPV invasion in patients with OED. As per the inclusion and exclusion criteria, this observational study included 180 patients with histologically confirmed oral epithelial dysplasia associated with leukoplakia or oral lichen planus. Interferon (IFN) status was assessed by measuring serum interferon activity, spontaneous interferon production, IFN-α/β, and IFN-γ activity in peripheral blood. HPV DNA was detected and genotyped in biopsy specimens using polymerase chain reaction. Results: HPV-positive patients demonstrated significantly lower IFN-α/β and IFN-γ activity compared with HPV-negative patients (p < 0.001). Severe OED was more frequently observed in HPV-positive individuals, whereas mild dysplasia predominated among HPV-negative patients (p < 0.05). Interferon activity progressively decreased with increasing dysplasia severity, with the lowest IFN-α/β and IFN-γ activity detected in patients with severe dysplasia (p < 0.001 and p < 0.05, respectively). A significant positive correlation between IFN-α/β and IFN-γ activity was identified in patients with moderate dysplasia (p = 0.003). Multivariate binary logistic regression analysis demonstrated that HPV positivity (adjusted OR = 4.62, 95% CI: 2.18–9.79; p < 0.001) and reduced IFN-α/β activity (adjusted OR = 1.34 per 10-unit decrease, 95% CI: 1.14–1.58; p < 0.001) were independently associated with severe dysplasia. The multivariable model demonstrated acceptable discriminatory ability for identifying patients with severe dysplasia (AUC = 0.736), with a sensitivity of 89.4% and a specificity of 56.1%. Conclusions: The findings suggest that HPV-associated OED is linked to reduced interferon status, particularly lower IFN-α/β and IFN-γ activity in more severe dysplastic lesions. Combined assessment of interferon status and HPV detection may help identify patients at higher risk of severe OED.
Full article
(This article belongs to the Special Issue Clinical Outcome Research in the Head and Neck: 2nd Edition)
►▼
Show Figures

Figure 1
Open AccessArticle
Age and Sex Influence the Neutrophil-to-Lymphocyte Ratio (NLR), a Systemic Inflammation Marker
by
Carmen Lara-Apolinario, Cesar Martinez-Carral, Desiree Fischetti, Adexe J. Fulgencio-González, Casimira Domínguez and Pedro C. Lara
Clin. Pract. 2026, 16(10), 178; https://doi.org/10.3390/clinpract16100178 - 24 Sep 2026
Abstract
►▼
Show Figures
Background/Objectives: The neutrophil-to-lymphocyte ratio (NLR), as a marker of systemic inflammation, has been studied in a wide variety of diseases. Unfortunately, there are very limited data describing the NLR distribution and reference intervals for a normal population in specific geographical areas. The
[...] Read more.
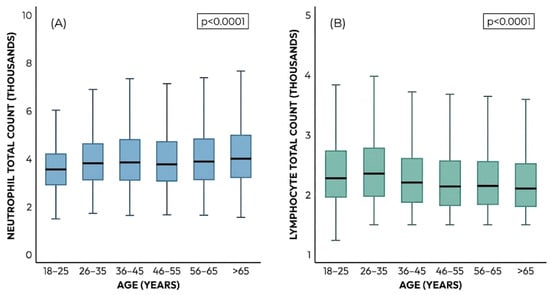
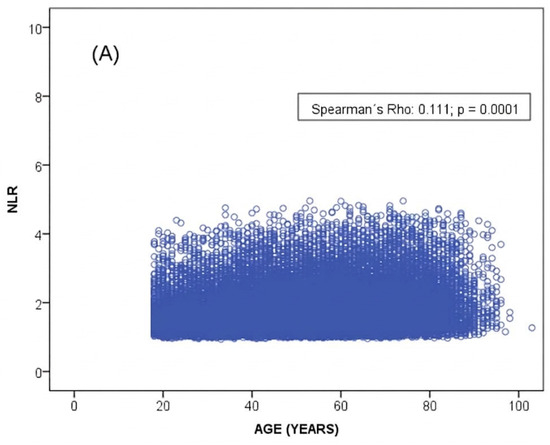
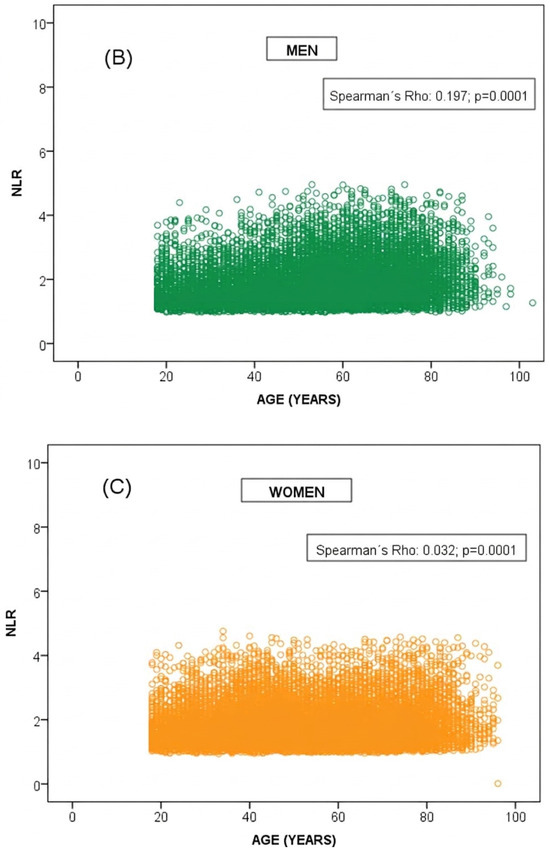
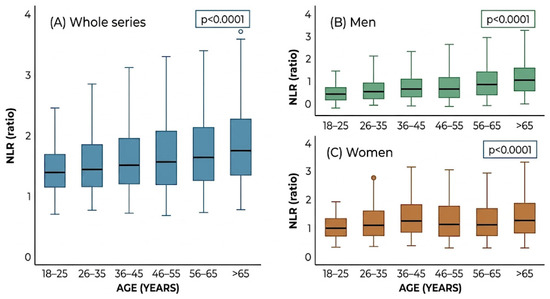
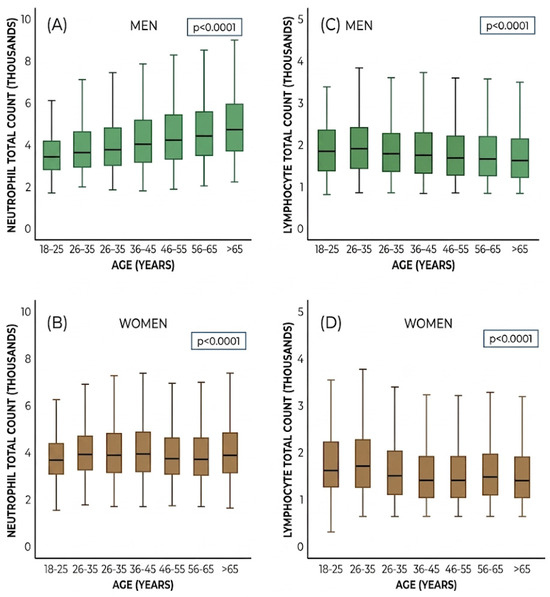
Background/Objectives: The neutrophil-to-lymphocyte ratio (NLR), as a marker of systemic inflammation, has been studied in a wide variety of diseases. Unfortunately, there are very limited data describing the NLR distribution and reference intervals for a normal population in specific geographical areas. The aim of this study was to analyze, for the first time, different patterns in NLR distribution, stratified by age and sex, in a large group of controls from a European country. Methods: Patients referred for a health examination to the Laboratory Department of Dr Negrín University Hospital from 1 January 2021 to 31 December 2025 were included in this study. The participants had normal hematological values, lipid metabolism markers and hepatic enzymes, erythrocyte sedimentation rates (ESRs), and C-reactive protein (CRP) levels. Samples were treated anonymously, including only sex and date of birth. The neutrophil-to-lymphocyte ratio (NLR) was determined by dividing the absolute neutrophil count by the absolute lymphocyte count. Results: A total of 30,676 controls were included in the study. NLR increased with age (p < 0.0001). Women showed lower NLR values than men (p < 0.0001), revealing an age-related pattern, with values increasing until age 45, dropping from 46 to 65, and slightly increasing in advanced age (>65 years). Conclusions: To our knowledge, this is the largest study from a European country analyzing the impact of sex and age on NLR values in controls. An interesting differential pattern of NLR modifications according to age group was observed in women. Therefore, NLR values must always be interpreted according to sex and age groups.
Full article

Figure 1
Open AccessArticle
The Lived Care Experiences of Neurorehabilitation Inpatients: A Phenomenological Qualitative Exploratory Study
by
Carlo Alberto Camuccio, Valeria Basso, Sara Guglielmi, Laura Danesin, Francesca Burgio, Enrico Dal Pozzo and Luisa Cacciante
Clin. Pract. 2026, 16(10), 177; https://doi.org/10.3390/clinpract16100177 - 24 Sep 2026
Abstract
Background and Aim: Hospitalization is increasingly seen as a key factor in rehabilitation outcomes, shaped by patient satisfaction, motivation, and relationships with staff. The lived experience of neurorehabilitation across neurological conditions, such as stroke, multiple sclerosis, Parkinson’s disease, and post-oncological care, remains largely
[...] Read more.
Background and Aim: Hospitalization is increasingly seen as a key factor in rehabilitation outcomes, shaped by patient satisfaction, motivation, and relationships with staff. The lived experience of neurorehabilitation across neurological conditions, such as stroke, multiple sclerosis, Parkinson’s disease, and post-oncological care, remains largely unknown. This study explores the care and hospitalization experience of individuals admitted to neurorehabilitation units with diagnoses of stroke, multiple sclerosis, Parkinson’s disease, and post-neurosurgical recovery following oncological procedures. Methods: Thirty-seven patients with neurological conditions were enrolled and interviewed. A descriptive phenomenological design was employed, using semi-structured interviews. Data were analyzed following Colaizzi’s method, supported by Atlas.ti 25. Phenomenological analysis was used to identify themes emerging from patient narratives, with rigor ensured through independent coding, triangulation, and saturation-based sampling. Results: Five themes emerged: (1) the therapeutic bond with healthcare professionals; (2) the slow time of hospitalization, marked by waiting and boredom; (3) care is rehabilitation; (4) illness narratives; and (5) stories of closeness among inpatients and family members. Conclusions: The results of this study highlight neurorehabilitation as a relational process. These findings reinforce the importance of considering patients’ experiences as an integral component of neurorehabilitation hospitalization. Future research should further explore how these dimensions may contribute to the development of more person-centered approaches to neurorehabilitation.
Full article
Open AccessReview
Beyond Reported Rates: A Critical Narrative Review of the Risk Architecture, Early Recognition, and Prevention of Complications in Gynecologic Laparoscopy
by
Rastko Maglic, Milica Ivanovic, Ksenija Lalic, Dragana Maglic, Jelena Stulic and Stefan Ivanovic
Clin. Pract. 2026, 16(10), 176; https://doi.org/10.3390/clinpract16100176 - 22 Sep 2026
Abstract
Reported complication rates in gynecologic laparoscopy are widely used as indicators of safety, yet they often describe fundamentally different clinical realities. Variations in definitions, severity classification, duration of follow-up, and procedural context mean that superficially similar outcomes are frequently not comparable. As a
[...] Read more.
Reported complication rates in gynecologic laparoscopy are widely used as indicators of safety, yet they often describe fundamentally different clinical realities. Variations in definitions, severity classification, duration of follow-up, and procedural context mean that superficially similar outcomes are frequently not comparable. As a result, the literature is rich in data, but limited in interpretability. This review addresses that gap by critically examining complications not only as events but as phenomena shaped by methodological heterogeneity, procedural complexity, and the conditions under which they are recognized. A search of PubMed/MEDLINE, Scopus, and Web of Science was performed, with additional manual reference screening. Given the predominance of heterogeneous retrospective series, cohort studies, registries, and targeted systematic reviews, a narrative synthesis was undertaken. Across studies, the most clinically significant complications remain hemorrhage, bowel injury, and urinary tract injury, while pneumoperitoneum-related events, vaginal cuff dehiscence, port-site complications, port-site metastasis, and morcellation-related dissemination represent rarer but disproportionately consequential outcomes. Importantly, complication risk consistently clusters around identifiable domains, including prior surgery and adhesions, procedural complexity, energy use, operative duration, surgeon experience, and center-level standardization. This review shows that complications in gynecologic laparoscopy cannot be meaningfully interpreted through incidence alone. Their true clinical significance lies in the interaction between risk architecture, intraoperative decision-making, and the timeliness of postoperative recognition. The principal contribution of this work is therefore not a single summary rate but a clinically oriented framework that integrates interpretation of the literature with practical principles of prevention and early diagnosis.
Full article
(This article belongs to the Section Reproductive Medicine and Women’s Health)
Open AccessArticle
Beyond Ejection Fraction: Inflammatory Risk and Mortality in Heart Failure
by
Bozhidar Krastev, Natalia Spasova, Desislava Somleva, Neli Georgieva, Slavi Yakov, Elena Kinova and Assen Goudev
Clin. Pract. 2026, 16(10), 175; https://doi.org/10.3390/clinpract16100175 - 22 Sep 2026
Abstract
Background: Inflammation is increasingly recognized as an important contributor to the progression of heart failure and may partly explain differences in prognosis beyond conventional clinical characteristics. Simple laboratory-based inflammatory indices may offer additional prognostic information, but their value across different heart failure phenotypes
[...] Read more.
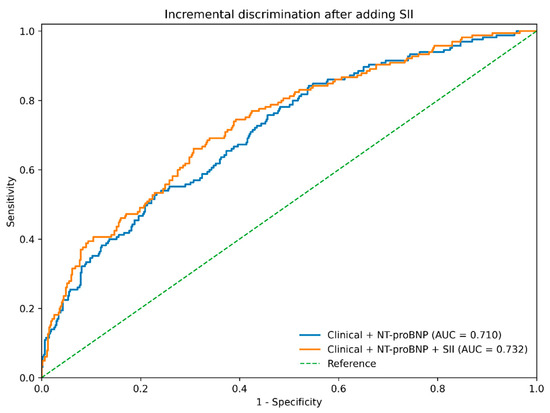
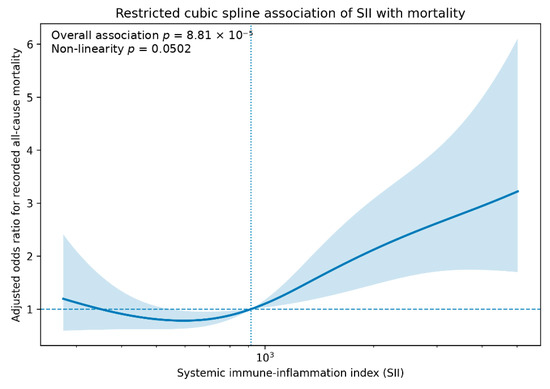
Background: Inflammation is increasingly recognized as an important contributor to the progression of heart failure and may partly explain differences in prognosis beyond conventional clinical characteristics. Simple laboratory-based inflammatory indices may offer additional prognostic information, but their value across different heart failure phenotypes remains uncertain. Objectives: To investigate the association between the systemic immune-inflammation index and recorded all-cause mortality across the spectrum of heart failure and to evaluate its incremental prognostic value beyond conventional clinical and laboratory variables. Patients and Methods: We evaluated the association between the systemic immune-inflammation index (SII) and recorded all-cause mortality in patients with heart failure. Multivariable logistic regression models included age, sex, heart failure phenotype, cardiovascular comorbidities, NT-proBNP, renal function, and hemoglobin. Model discrimination and calibration were assessed, and additional analyses evaluated multicollinearity, interaction with heart failure phenotype, and the functional form of the association. Results: Among 637 patients, mortality status was available for 634, of whom 165 died (26.0%). After multivariable adjustment, each doubling of SII was associated with higher odds of recorded all-cause mortality (OR 1.42, 95% CI 1.19–1.70; p < 0.001). Previous myocardial infarction, atrial fibrillation, and NT-proBNP also remained independently associated with mortality, whereas LVEF phenotype was not. No significant interaction was observed between SII and heart failure phenotype. Adding SII improved overall model fit (likelihood-ratio χ2 = 16.17; p < 0.001) and increased the AUC from 0.710 to 0.732, although the difference in discrimination was not statistically significant (DeLong p = 0.076). There was no convincing evidence of marked non-linearity. Conclusions: A higher systemic inflammatory burden was independently associated with recorded all-cause mortality across the heart failure spectrum. This readily available marker may provide complementary prognostic information, but its incremental value appears modest. External validation is needed before it can be considered for routine risk assessment.
Full article
(This article belongs to the Special Issue Heart Failure: Current Trends and Future Directions)
►▼
Show Figures

Figure 1
Open AccessArticle
Antiproteinuric Response to Finerenone in Diabetic Kidney Disease: Responder and Non-Responder Subgroup Analysis of the FINDKDLATAM Study
by
Jorge Rico Fontalvo, María Raad Sarabia, José C. De La Flor, Vicente Sánchez Polo, Jenniffer Benavides Garcia, Enrique Ramos Clason, Daniel Domínguez, Giovanny Mera Rebutti, Carlos Madrid Mancia, Rene Tabora López, Manuel Rocha Meza, Dany Tabora López, James J. Muñoz Zambrano, Eduardo Lorca Herrera, Eliana Dina-Batlle, Michael Cieza Terrones, Alvaro Pedroza Pallares, Tomas Rodríguez Yánez, Washington Osorio, Alyi Arellano Cabeza, Juan Felipe Gutiérrez, Avinash Chandu Nanwani, Celia Rodríguez Tudero and Rodrigo Daza Arnedoadd
Show full author list
remove
Hide full author list
Clin. Pract. 2026, 16(10), 174; https://doi.org/10.3390/clinpract16100174 - 22 Sep 2026
Abstract
►▼
Show Figures
Background/Objectives: Albuminuria is an early marker of kidney damage and an independent predictor of adverse outcomes, making its reduction a key therapeutic goal. Finerenone, a selective nonsteroidal mineralocorticoid receptor antagonist, has demonstrated renal and cardiovascular benefits in patients with diabetic kidney disease
[...] Read more.
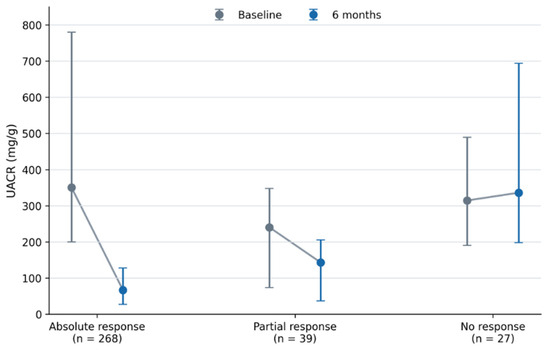
Background/Objectives: Albuminuria is an early marker of kidney damage and an independent predictor of adverse outcomes, making its reduction a key therapeutic goal. Finerenone, a selective nonsteroidal mineralocorticoid receptor antagonist, has demonstrated renal and cardiovascular benefits in patients with diabetic kidney disease (DKD), although the magnitude of the antiproteinuric response may vary in clinical practice. This post hoc analysis aimed to characterize the six-month antiproteinuric response to finerenone and to descriptively explore baseline clinical and treatment characteristics across response categories in the FINDKDLATAM cohort. Methods: A subgroup analysis was performed on a real-world, multicenter, retrospective, observational study that included patients from the FINDKDLATAM study who had urinary albumin-to-creatinine ratio (UACR) measurements taken at baseline and six months. Patients were classified as absolute responders (≥50% reduction in UACR), partial responders (30–49% reduction), and non-responders (<30% reduction or no reduction in UACR) at six months of follow-up. Sociodemographic, clinical, biochemical, therapeutic, and safety variables were analyzed. Results: Of the 347 patients included in the original cohort, 334 had complete UACR data at six months and were included in the analysis. Of these, 80.2% (n = 268) were absolute responders, 11.7% (n = 39) partial responders, and 8.1% (n = 27) non-responders. Median UACR decreased from 350.7 to 67.0 mg/g among absolute responders and from 240.5 to 143.0 mg/g among partial responders (both p < 0.0001), whereas no significant change was observed among non-responders. No baseline clinical characteristic consistently distinguished responders from non-responders. Serum potassium increased during follow-up, particularly among non-responders. Conclusions: In this retrospective Latin American cohort, most patients experienced a reduction in UACR after six months of finerenone treatment. However, the uncontrolled observational design, concomitant therapies, UACR variability, and regression to the mean preclude attributing these changes exclusively to finerenone. These exploratory findings do not support selecting patients according to a particular responder phenotype but rather support prescribing finerenone according to currently approved clinical criteria. Prospective studies with adjusted analyses are needed to identify independent predictors of response.
Full article

Figure 1
Open AccessArticle
Patterns of Detecting Substances of Abuse in a Large Series of Patients in Spain During 2021–2025
by
Carmen Lara-Apolinario, Cesar Martinez-Carral, Desiree Fischetti, Adexe J. Fulgencio-González, Casimira Domínguez and Pedro C. Lara
Clin. Pract. 2026, 16(9), 173; https://doi.org/10.3390/clinpract16090173 - 21 Sep 2026
Abstract
►▼
Show Figures
Aim: This study was conducted to assess, for the first time, patterns in common drugs of abuse detected in urine samples from a large series of patients treated at a tertiary university hospital and the role of age and sex in these patterns.
[...] Read more.
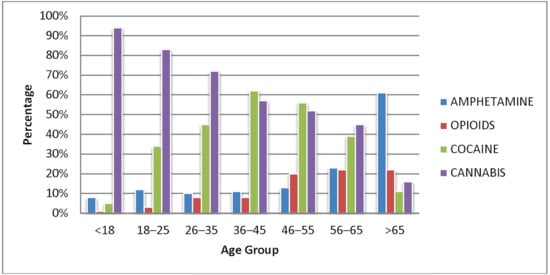
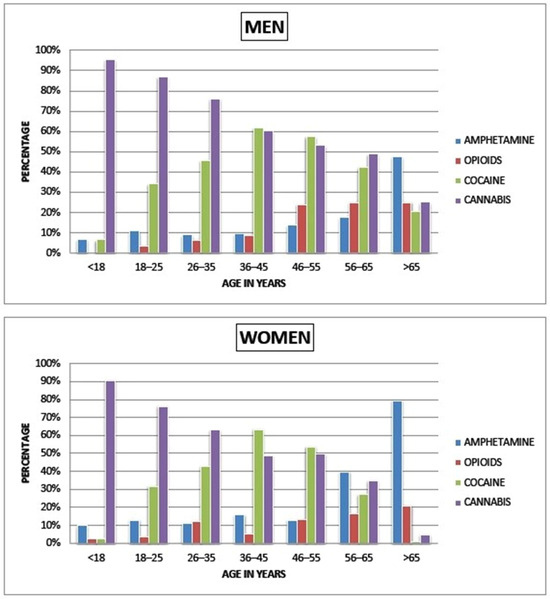
Aim: This study was conducted to assess, for the first time, patterns in common drugs of abuse detected in urine samples from a large series of patients treated at a tertiary university hospital and the role of age and sex in these patterns. Methods: This study included samples from all patients analyzed at the Dr. Negrín University Hospital Laboratory from January 2021 to December 2025 with positive immunoassay test results for at least one of the following substances of abuse: cannabis, cocaine, amphetamine/methamphetamine, or opioids. The samples were anonymized, and only the patient’s sex and date of birth were included in the analysis. Results: In total, there were 5019 positive results for at least one of the substances screened (cannabis, opioids, amphetamine, or cocaine). Women represented only 28.2% of all patients with a positive test (p < 0.0001). Substance positivity was strongly influenced by age. Cannabis positivity was observed in 2989 cases (59.9%) and was very high in the younger age groups, consistently declining towards age 65 (94% for <18 years vs. 16.2% for >65 years) (p < 0.0001). In contrast, amphetamine (15.9%) and opioid (13.9%) use rose consistently from 7.5% and 0.7%, respectively, among patients aged <18 years, to 61.3% and 23.1%, respectively, in the >65 age group (p < 0.0001). Cocaine positivity (45.6%) was very low at early ages (5.4% for <18 years group), increased in middle age (62%: 36–55 years group), and decreased in older age (11.9% for >65 years group) (p < 0.0001). Conclusions: With more than five thousand samples analyzed, our study sheds light on the profile of substance abuse in a large population of patients attending a university hospital. Our results can help to better adjust preventive political actions and medical care, in the context of substance abuse.
Full article

Figure 1
Open AccessCase Report
Paget–Schrotter Syndrome in the Primary Care Setting: A Case Report and Scoping Review of Clinical Presentation and Diagnostic Delay
by
Mohammed Hteit, Raein Ghazvinian and Mohammed Abdulrasak
Clin. Pract. 2026, 16(9), 172; https://doi.org/10.3390/clinpract16090172 - 19 Sep 2026
Abstract
►▼
Show Figures
Background/Objectives: Paget–Schrotter syndrome (PSS), or primary axillary-subclavian vein thrombosis, is an uncommon but clinically important form of upper extremity deep vein thrombosis. It often affects young, physically active patients and may initially be interpreted as a musculoskeletal disorder. This scoping review, combined with
[...] Read more.
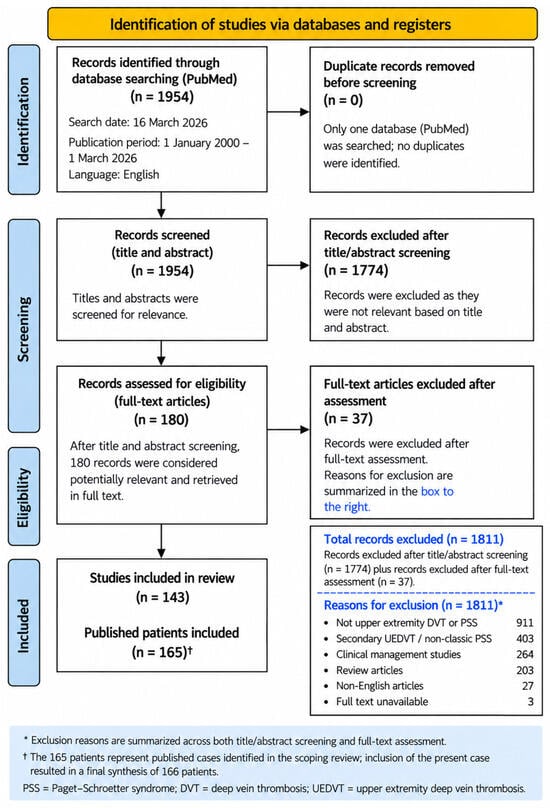
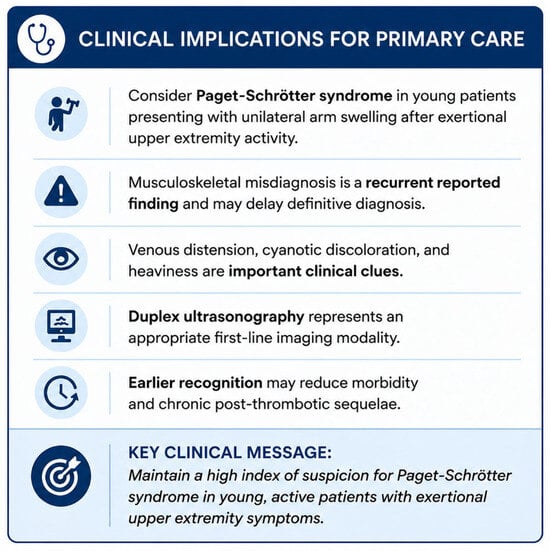
Background/Objectives: Paget–Schrotter syndrome (PSS), or primary axillary-subclavian vein thrombosis, is an uncommon but clinically important form of upper extremity deep vein thrombosis. It often affects young, physically active patients and may initially be interpreted as a musculoskeletal disorder. This scoping review, combined with a contemporary primary care case, aimed to map the reported clinical presentation, diagnostic delay, and initial misdiagnosis of classic PSS. Methods: The review was conducted using the Arksey and O’Malley framework and reported in accordance with the PRISMA extension for scoping reviews (PRISMA-ScR). PubMed was searched for English-language publications from 1 January 2000 to 1 March 2026. Eligible reports described effort-induced thrombosis involving the axillary and/or subclavian venous segment. Secondary upper extremity deep vein thrombosis, non-effort thrombosis, pseudo-PSS, isolated distal venous thrombosis, and reports without extractable patient-level presentation data were excluded. Data were charted descriptively. Results: Among 1954 screened records, 143 studies met inclusion criteria and contributed 165 published patients. Together with the present case, the synthesis included 166 patients. Median age was 28 years, and 73.5% were male. Arm swelling (95.2%), pain (80.1%), cyanosis or discoloration (69.9%), and venous distension (70.5%) were the most frequent presenting features. Diagnostic delay was reported in 27.3% of patients with reported data, whereas initial misdiagnosis was reported in 21.7% of included patients. Musculoskeletal injury or muscle strain was the most common initial misdiagnosis, accounting for 66.7% of misdiagnosed cases. Pulmonary embolism was reported in 24.7% of patients, although this reported frequency is likely influenced by case-report publication bias, selective imaging, and preferential reporting of more severe presentations, and should not be interpreted as a population-level risk estimate. Conclusions: PSS should be considered in young or otherwise low-risk patients with unilateral arm swelling after strenuous or repetitive upper extremity activity. Greater awareness of this clinical presentation in primary care and general emergency settings may reduce diagnostic delay and post-thrombotic morbidity.
Full article

Figure 1
Open AccessArticle
The Effect of the COVID-19 Pandemic on Myocardial Infarction Care in Kosovo
by
Zarife Rexhaj, Besfort Kryeziu, Premtim Rashiti, Pranvera Ibrahimi, Arlind Batalli, Afrim Poniku, Margaritë Gjoka, Michael Henein, Shpend Elezi and Gani Bajraktari
Clin. Pract. 2026, 16(9), 171; https://doi.org/10.3390/clinpract16090171 - 18 Sep 2026
Abstract
Background and Aim: Studies worldwide have documented a reduction in acute myocardial infarction (AMI) admissions during the COVID-19 pandemic. We aimed to assess AMI admissions, management, and in-hospital outcomes in Kosovo during the pandemic period. Methods: We conducted a retrospective single-centre study including
[...] Read more.
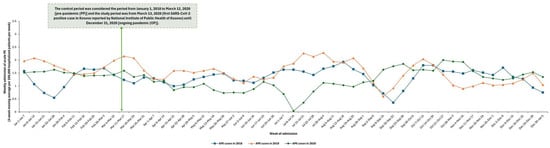
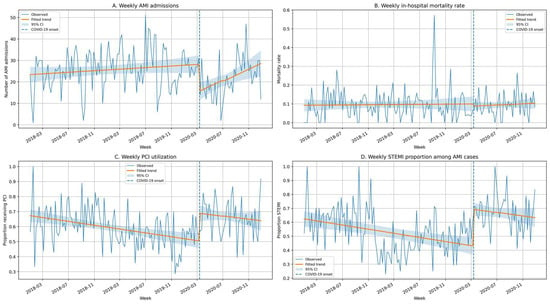
Background and Aim: Studies worldwide have documented a reduction in acute myocardial infarction (AMI) admissions during the COVID-19 pandemic. We aimed to assess AMI admissions, management, and in-hospital outcomes in Kosovo during the pandemic period. Methods: We conducted a retrospective single-centre study including all consecutive AMI admissions from 1 January 2018 to 31 December 2020 at the Clinic of Cardiology, University Clinical Centre of Kosovo, the only public tertiary primary percutaneous coronary intervention (PCI) centre in the country. The pre-pandemic (PP) period was defined as 1 January 2018–12 March 2020 and the ongoing pandemic (OP) period as 13 March–31 December 2020. Demographic, clinical, laboratory, angiographic, and outcome data were collected. In-hospital mortality was defined as death between admission and discharge. Interrupted time-series analyses were performed. Results: A total of 898 AMI patients were admitted during OP and 2955 during PP. Daily admissions decreased from 3.8/day to 3.05/day (p < 0.001). OP patients were younger, more often hypertensive and smokers, and more frequently male. Coronary angiography (81% vs. 76%, p = 0.001) and PCI (66% vs. 60%, p = 0.001) were more frequent during OP, while in-hospital mortality remained unchanged. Time-series analysis showed a sharp fall in admissions at OP (β = −12.66, p < 0.001) with gradual recovery, alongside an increase in PCI use (β = 0.184, p < 0.001) and stable mortality. The proportion of ST-segment elevation (STEMI) cases increased significantly during the pandemic period. Compared with the pandemic period, admission during the pre-pandemic period was associated with lower odds of undergoing PCI (aOR 0.81, 95% CI 0.69–0.95), while age ≥ 65 reduced the likelihood of PCI. Conclusions: AMI hospitalizations in Kosovo declined significantly during the COVID-19 pandemic. The pandemic cohort was younger, with the profile of admitted patients shifting toward younger age, male sex, and STEMI presentation. Despite fewer admissions, PCI use increased, while no statistically significant difference in in-hospital mortality was observed between the two periods. These findings describe changes in treatment patterns and short-term in-hospital outcomes during the pandemic but should not be interpreted as evidence of equivalent overall quality of AMI care.
Full article
(This article belongs to the Section Cardiac and Cardiovascular Systems)
►▼
Show Figures

Figure 1
Open AccessArticle
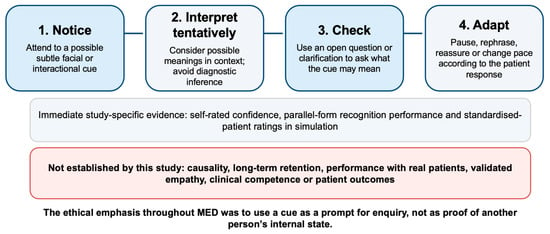
The Micro-Expression Decoder: A Preliminary Mixed-Methods Evaluation of Training in Subtle Facial and Non-Verbal Cue Recognition in Final-Year Medical Students
by
Hashira Syed, Katerina Sini, Andreas Conte, Austen El-Osta, Azeem Majeed and Waseem Jerjes
Clin. Pract. 2026, 16(9), 170; https://doi.org/10.3390/clinpract16090170 - 14 Sep 2026
Abstract
►▼
Show Figures
Background/Objectives: Subtle facial and interactional cues may prompt clinicians to explore possible anxiety, confusion or hesitation, but they do not establish a patient’s internal state. The Micro-Expression Decoder (MED) links cue recognition with tentative interpretation, direct checking and communication adaptation. Methods:
[...] Read more.
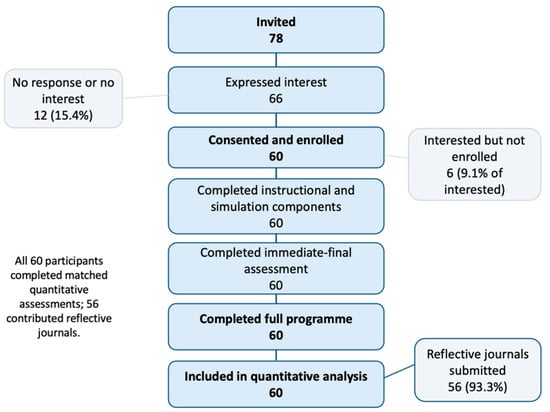
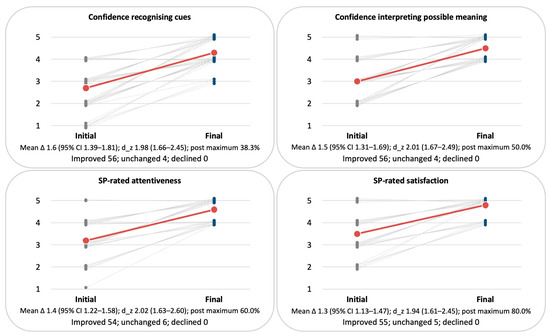
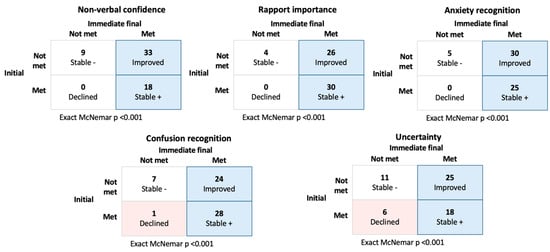
Background/Objectives: Subtle facial and interactional cues may prompt clinicians to explore possible anxiety, confusion or hesitation, but they do not establish a patient’s internal state. The Micro-Expression Decoder (MED) links cue recognition with tentative interpretation, direct checking and communication adaptation. Methods: This preliminary, uncontrolled, single-group pre–post convergent mixed-methods evaluation involved 60 final-year medical students from three London medical schools. Ten groups of six completed a 270 min simulation-based programme comprising conceptual teaching, video observation, standardised-patient encounters, feedback and reflection. Study-specific self-ratings and a parallel-form recognition task were completed before teaching and immediately after the instructional and simulation components, before the final debrief. Standardised-patient ratings were obtained during the first and final simulated encounters. There was no control group or follow-up. Results: Recognition confidence increased from 2.7 to 4.3 (mean change 1.6, 95% CI 1.39–1.81; dz = 1.98), interpretation confidence from 3.0 to 4.5 (dz = 2.01), standardised-patient-rated attentiveness from 3.2 to 4.6 (dz = 2.02), and satisfaction from 3.5 to 4.8 (dz = 1.94). Anxiety recognition increased from 25/60 (41.7%) to 55/60 (91.7%), and confusion recognition from 29/60 (48.3%) to 52/60 (86.7%). Qualitative accounts described earlier noticing, clarification and checking, alongside difficulty distinguishing cues, distraction, cultural variation and over-interpretation. Nineteen students increased confidence without categorical improvement in anxiety or confusion recognition. Conclusions: MED was associated with immediate improvement across study-specific outcomes in simulation. The uncontrolled design, immediate assessment, investigator-developed measures, expectancy effects and ceiling in post-training satisfaction preclude conclusions about causality, retention, real-patient benefit, empathy or clinical competence.
Full article

Figure 1
Open AccessArticle
Factors Associated with Prolonged Hospitalisation in Women with Breast Cancer: Evidence from a Large German Multicentre Study
by
Lisa Cordes, Karel Kostev and Matthias Kalder
Clin. Pract. 2026, 16(9), 169; https://doi.org/10.3390/clinpract16090169 - 11 Sep 2026
Abstract
►▼
Show Figures
Background/Objectives: Breast cancer is the most common malignancy among women worldwide and poses a significant burden on healthcare systems. Despite evidence that treatment type is associated with hospital length of stay (LOS), current Germany-wide data on this topic are lacking. The present
[...] Read more.
Background/Objectives: Breast cancer is the most common malignancy among women worldwide and poses a significant burden on healthcare systems. Despite evidence that treatment type is associated with hospital length of stay (LOS), current Germany-wide data on this topic are lacking. The present study aims to identify clinical and procedural factors associated with prolonged hospitalisation in women hospitalised for breast cancer in Germany. Methods: This multicentre cross-sectional study analysed anonymised inpatient data from 38 German hospitals (IQVIA database), including 16,062 female breast cancer hospitalisation episodes (inpatient cases; patient-level linkage was not possible due to anonymisation, so these may not represent 16,062 distinct women) treated between January 2019 and December 2024. The primary outcome was LOS; prolonged hospitalisation was defined as LOS > 7 days (75th percentile). Comorbidities were assessed using individual comorbidity categories defined according to the Elixhauser classification (retained at ≥1% prevalence). The primary multivariable analysis was restricted to characteristics documented independently of the in-hospital course (age, tumour site, metastatic status, chronic comorbidities). In-hospital complications, procedures, and diagnoses of ambiguous timing were analysed separately as secondary, descriptive associations. LOS was modelled using negative binomial regression (Poisson regression as a sensitivity analysis) and prolonged LOS using logistic regression, both with hospital-clustered robust (sandwich) standard errors. Results: The overall median LOS was 4 days (IQR 3–7); 19.3% of hospitalisation episodes were prolonged. In the primary analysis, longer LOS was associated with age > 70 years (RR 1.14; 95% CI 1.08–1.20), distant metastases (RR 1.76; 95% CI 1.51–2.04), lymph node metastases (RR 1.09; 95% CI 1.05–1.12), congestive heart failure (RR 1.44; 95% CI 1.31–1.59), anaemia (RR 1.41; 95% CI 1.14–1.75) and depression (RR 1.14; 95% CI 1.03–1.26). In the secondary descriptive analysis, in-hospital complications showed the strongest associations with longer LOS, particularly postoperative infection (RR 2.28), wound disruption (RR 1.92) and pneumonia (RR 1.45). Breast-conserving surgery and partial breast resection were associated with shorter LOS, while mastectomy, blood transfusions, and complex intensive care were associated with prolonged stays; the small inpatient radiotherapy subgroup (1.9%) most likely reflects a highly selected, predominantly palliative population rather than an association attributable to radiotherapy itself. Conclusions: Prolonged hospitalisation was associated with older age, documented lymph node and distant metastases, and chronic somatic comorbidities including congestive heart failure, anaemia, chronic kidney disease and depression, and, in secondary descriptive analyses, with perioperative complications and intensive procedures. The strongest correlates of prolonged stay—in-hospital complications and intensive procedures—are documented during rather than before the hospitalisation and therefore cannot themselves support early risk identification; however, the baseline characteristics documented independently of the in-hospital course (age, metastatic disease, chronic comorbidity burden) may usefully inform structured perioperative management and discharge planning in Germany.
Full article

Figure 1
Open AccessCase Report
Recurrent Pleomorphic Adenoma of the Palate: A Case Report
by
Evangelos Kostares, Stavroula Diamantopoulou, Ourania Schoinohoriti, Georgia Kostare, Ioli Artopoulou, Georgios Mitsopoulos and Christos Perisanidis
Clin. Pract. 2026, 16(9), 168; https://doi.org/10.3390/clinpract16090168 - 10 Sep 2026
Abstract
Background: Pleomorphic adenoma is the most common benign salivary-gland neoplasm and frequently affects the minor salivary glands of the palate. Although surgical excision is generally curative, incomplete encapsulation, pseudopod-like extensions, and microscopic tumor deposits may contribute to recurrence, which can occur many years
[...] Read more.
Background: Pleomorphic adenoma is the most common benign salivary-gland neoplasm and frequently affects the minor salivary glands of the palate. Although surgical excision is generally curative, incomplete encapsulation, pseudopod-like extensions, and microscopic tumor deposits may contribute to recurrence, which can occur many years after initial treatment. Recurrent palatal pleomorphic adenoma is uncommon and may present diagnostic and reconstructive challenges. Case Presentation: A 64-year-old man was referred with a painless, slowly enlarging recurrent mass of the right posterior hard palate, six years after excision of a pleomorphic adenoma at another institution. Magnetic resonance imaging and contrast-enhanced computed tomography demonstrated a well-defined enhancing palatal lesion measuring approximately 2.1 × 1.9 × 1.9 cm on MRI and 1.8 × 2.2 × 1.9 on CT, without adjacent maxillary bone destruction or cervical lymphadenopathy. An incisional biopsy was consistent with pleomorphic adenoma. Wide local excision was performed, including the tumor, surrounding palatal soft tissue, and underlying periosteum. The resulting defect was reconstructed using a facial artery musculomucosal flap. The postoperative course was uneventful, with satisfactory flap healing and preservation of speech and swallowing. At six months of follow-up, there was no clinical evidence of recurrence or functional impairment. Conclusions: Recurrent pleomorphic adenoma of the palate may develop several years after primary treatment. Complete surgical excision with tumor-free margins and appropriate reconstruction is essential. Long-term clinical follow-up is recommended because late recurrence and, rarely, malignant transformation may occur.
Full article
(This article belongs to the Special Issue Clinical Outcome Research in the Head and Neck: 2nd Edition)
►▼
Show Figures

Figure 1
Open AccessArticle
The Intrathecal Analgesia in Robotic Surgery (IARS) Study: Real-World Associations with Intraoperative Opioid Exposure, Fluid Administration, and Postoperative Pain-Free Recovery
by
Antonio Romanelli, Antonella Langone, Angela Rosaria Caccavale, Alberto D’Amicantonio, Mariafidelia Ferrara and Renato Gammaldi
Clin. Pract. 2026, 16(9), 167; https://doi.org/10.3390/clinpract16090167 - 9 Sep 2026
Abstract
Background/Objectives: Subarachnoid analgesia (SA) is increasingly used as an adjunct to general anesthesia in robotic ERAS pathways, but the contribution of the intrathecal local anesthetic, as distinct from that of the intrathecal opioids, has not been isolated. Methods: This study comprised a single-center
[...] Read more.
Background/Objectives: Subarachnoid analgesia (SA) is increasingly used as an adjunct to general anesthesia in robotic ERAS pathways, but the contribution of the intrathecal local anesthetic, as distinct from that of the intrathecal opioids, has not been isolated. Methods: This study comprised a single-center retrospective cohort of adults undergoing elective robotic surgery (May 2024–July 2025). The exposure was the intrathecal regimen, serving as mutually exclusive categories. The primary outcome was intraoperative opioid exposure (model-derived area under the concentration–time curve per hour, AUC/h); secondary outcomes were standardized intraoperative fluid administration and a stringent pain-free 48 h course (NRS = 0 throughout). Multivariable Gamma and logistic models were supplemented by provider-adjusted mixed-effects analyses, E-values, and a model-free robustness analysis. Results: Of 207 patients, 83.1% received SA; all were given intrathecal morphine and 62.3% levobupivacaine. Compared with no SA, morphine alone was not associated with AUC/h (+14.0%; 95% CI, −0.9 to +31.1), whereas all levobupivacaine-containing regimens were: −36.4% (IM + L5), −24.3% (IM + L5 + S3), and −44.8% (IM + L10 + S3); overall p < 0.001. Algebraically equivalent component reparameterization attributed this to levobupivacaine dose (−44.3% at 5 mg; −59.3% at 10 mg). Remifentanil was used in 98.7%, 88.6%, and 10.0% of patients receiving 0, 5, and 10 mg, respectively. Fluid administration was lower with IM + L5 (−24.9%) and IM + L10 + S3 (−31.0%) after adjustment, but was not with levobupivacaine-graded unadjustment. SA was associated with a pain-free course (adjusted OR, 3.33; 95% CI, 1.06–11.79), an estimate not robust to minimal unmeasured confounding. Conclusions: Levobupivacaine-containing regimens were consistently associated with lower intraoperative opioid exposure, but regimen and opioid strategy were chosen jointly by the same clinician; therefore, these associations between strategies are specific to the delivery context of this study. The fluid and pain-free findings are hypothesis-generating. Trials should vary the local anesthetic dose independently of intrathecal opioids.
Full article
(This article belongs to the Section Clinical Anesthesiology)
►▼
Show Figures

Figure 1
Open AccessSystematic Review
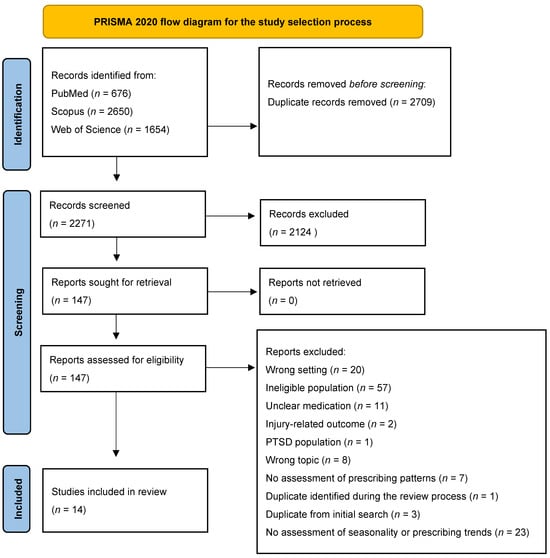
Primary Care Prescribing Patterns for Benzodiazepines and Z-Drugs, and Evidence Gaps Concerning Hydroxyzine and Seasonality: A Systematic Review
by
Małgorzata Romaszko, Anita Nowacka and Michał Majewski
Clin. Pract. 2026, 16(9), 166; https://doi.org/10.3390/clinpract16090166 - 9 Sep 2026
Abstract
►▼
Show Figures
Introduction: Medications with sedative and hypnotic properties, such as benzodiazepines, the so-called ‘Z-drugs’, and hydroxyzine, are used in primary care. However, data regarding their prescribing patterns, particularly in the context of seasonality, remain limited. Aim: This review aims to assess the current knowledge
[...] Read more.
Introduction: Medications with sedative and hypnotic properties, such as benzodiazepines, the so-called ‘Z-drugs’, and hydroxyzine, are used in primary care. However, data regarding their prescribing patterns, particularly in the context of seasonality, remain limited. Aim: This review aims to assess the current knowledge regarding primary care prescribing patterns for medications with potential sedative and hypnotic effects, with particular emphasis on benzodiazepines, ‘Z-drugs’, and hydroxyzine. Material and Methods: The systematic review was conducted following the PRISMA guidelines. The PubMed, Web of Science and Scopus databases were searched. Fourteen original English-language publications from 2015 to 2026, which focused on the primary care prescription of selected groups of medications with hypnotic properties, were included. Results: Most of the studies included concerned benzodiazepines, with inconsistent prescribing patterns. Some studies reported a decrease in the rate of their prescription, whilst others indicated an increase, particularly among older people and patients with multimorbidity. Data concerning ‘Z-drugs’ were less extensive and showed heterogeneous prescribing trends across countries and study periods. Overall, the findings indicate substantial international variability in hypnotic prescribing in primary care. Evidence regarding hydroxyzine prescribing was particularly limited, with only one study specifically examining its prescribing patterns in primary care. Data on the seasonal prescribing patterns for all groups of medications were limited. Conclusions: Prescription of medications with sedative and hypnotic properties remains an important part of primary healthcare practice. Yet, significant research gaps remain regarding hydroxyzine prescribing and the seasonal variation in hypnotic and sedative prescribing.
Full article

Figure 1
Open AccessOpinion
Quality Assurance in Laparoscopic Gynecological Training: A Narrative Review of Standards with a Multicenter Expert Perspective on Pathways Toward Effective Education and Care
by
Vlad Iustin Tica, Liliana Steriu, Dragos Brezeanu, Andrei A. Tica, Ana-Maria Brezeanu, Diana Badiu, Roxana Penciu, Silvia Onuc, Irina Tica and Maya Sophie de Wilde
Clin. Pract. 2026, 16(9), 165; https://doi.org/10.3390/clinpract16090165 - 5 Sep 2026
Abstract
►▼
Show Figures
Background: Quality assurance (QA) is a cornerstone of safe and effective postgraduate training in gynecological laparoscopic surgery, where clinical outcomes depend on procedural complexity, equipment sophistication, and the coordinated competence of an entire surgical team. This article is a narrative review of the
[...] Read more.
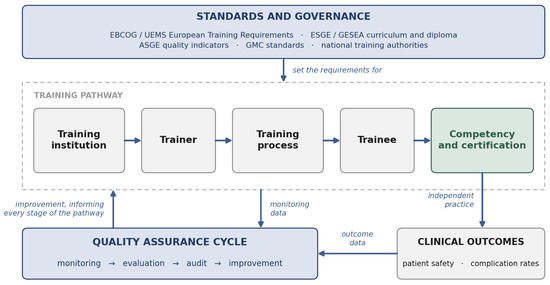
Background: Quality assurance (QA) is a cornerstone of safe and effective postgraduate training in gynecological laparoscopic surgery, where clinical outcomes depend on procedural complexity, equipment sophistication, and the coordinated competence of an entire surgical team. This article is a narrative review of the conceptual, professional, and regulatory foundations of QA in healthcare education, complemented by a structured synthesis of the collective teaching and clinical experience of the author group. It is not an empirical study, and the sections that follow present a conceptual mapping supported by expert perspective rather than original outcome data. Methods: Sources were identified through targeted searches of PubMed/MEDLINE and Google Scholar, supplemented by hand-searching of policy and curriculum documents issued by professional bodies and by backward citation tracking, without date restriction. Approximately 480 records were screened at title and abstract level, 112 were assessed as full text, and 41 sources were retained against predefined inclusion and exclusion criteria, with five further sources added during peer review. In a second and separate step, the ten co-authors, who hold teaching and supervisory roles in gynecological laparoscopy across academic centers in Romania and Germany, each completed the same six-item written prompt on training provision, trainer development, trainee assessment, and institutional QA practice; responses were coded thematically by two authors independently and consolidated into explicit points of convergence and divergence. Results: We describe how QA principles, originally articulated in general quality-management and health-promotion literature, have been adapted by professional and regulatory bodies, including the European Board and College of Obstetrics and Gynecology (EBCOG), European Society for Gynecological Endoscopy (ESGE), American Society for Gastrointestinal Endoscopy (ASGE), and the UK General Medical Council, into concrete standards for training providers, trainers, and trainees. We outline the structures used to monitor and audit training quality, including Kirkpatrick’s four-level evaluation model and periodic institutional review cycles, alongside documentation and certification pathways such as the Gynecological Endoscopic Surgical Education and Assessment (GESEA) program, with governance and financing as cross-cutting determinants of sustainability. The author synthesis converged on a consistent gap between documented standards and their routine enforcement and diverged on whether external review and formal certification should become mandatory. Conclusions: The conceptual architecture of QA in gynecological laparoscopy is coherent and broadly fit for purpose, but we identified no study linking the implementation of a specific QA standard to measurable gains in trainee competency or patient outcomes in this field. Proposals for harmonized, outcome-oriented, and where appropriate, mandatory external review should therefore be read as reasoned positions awaiting prospective evaluation rather than as evidence-based recommendations; generating that evidence, with the trainee’s own perspective collected rather than inferred, is the principal task for future research.
Full article

Figure 1
Open AccessArticle
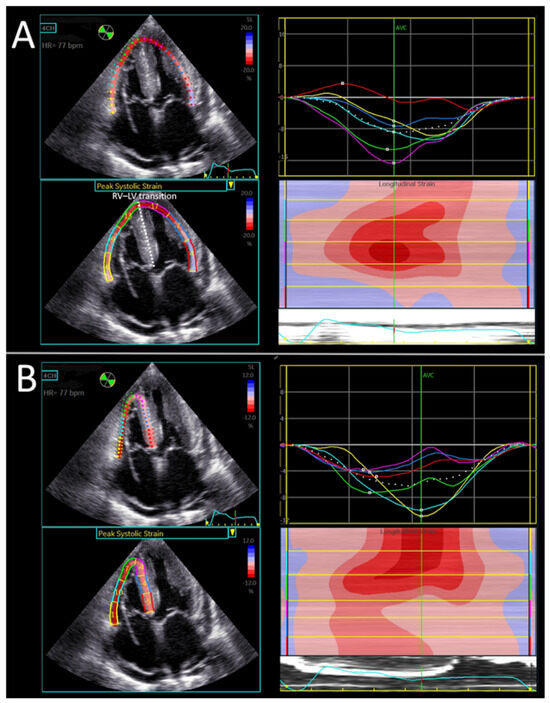
An Alternative Biventricular Tracking Approach for Assessment of Right Ventricular Strain in Cardiac Amyloidosis
by
Marina Leitman, Vladimir Tyomkin and Shmuel Fuchs
Clin. Pract. 2026, 16(9), 164; https://doi.org/10.3390/clinpract16090164 - 4 Sep 2026
Abstract
Background: Cardiac amyloidosis is characterized by progressive myocardial infiltration leading to ventricular dysfunction. While left ventricular strain assessment is well established, evaluation of right ventricular (RV) mechanics remains challenging because of the ventricle’s complex geometry and limitations of conventional speckle-tracking methods. We aimed
[...] Read more.
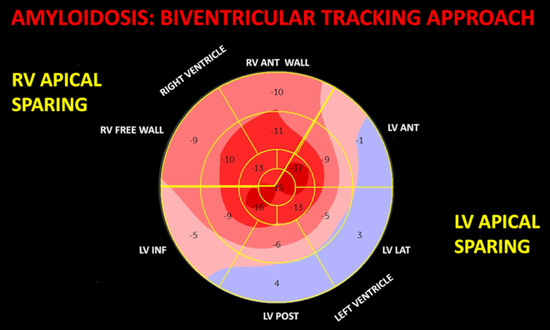
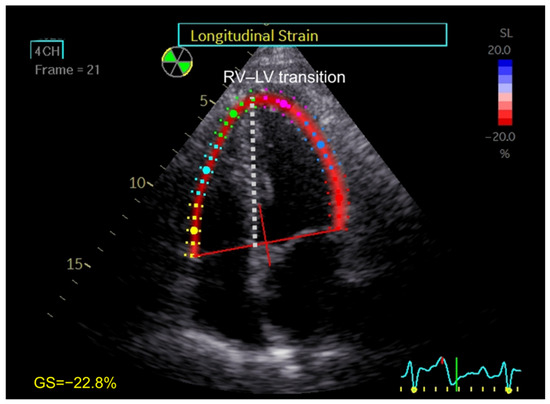
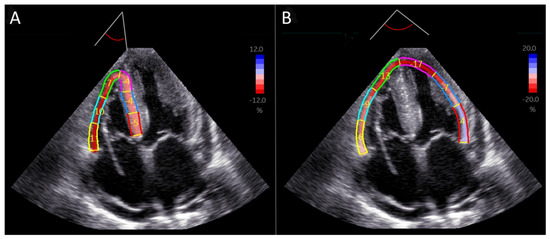
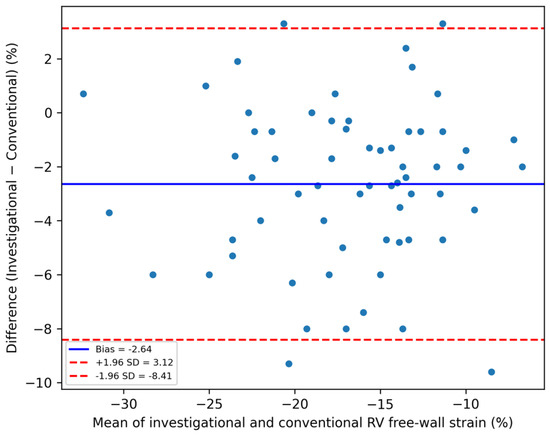
Background: Cardiac amyloidosis is characterized by progressive myocardial infiltration leading to ventricular dysfunction. While left ventricular strain assessment is well established, evaluation of right ventricular (RV) mechanics remains challenging because of the ventricle’s complex geometry and limitations of conventional speckle-tracking methods. We aimed to evaluate an alternative approach for RV strain assessment based on a continuous biventricular tracking pathway within the apical four-chamber view. Methods: We retrospectively studied 32 patients with cardiac amyloidosis and 32 age-, sex-, rhythm-, and ejection fraction–matched controls. RV free-wall longitudinal strain was measured using a novel investigational biventricular tracking approach from the basal RV free wall through the apex to the basal lateral left ventricular wall and compared with conventional RV strain. Investigational biventricular strain (BVS) was also obtained automatically as a surrogate marker of global ventricular function. Reproducibility was assessed in a subset of 20 patients using intraclass correlation coefficients (ICC), coefficient of variation (CV), and Bland–Altman analysis. Results: Investigational RV free-wall strain was significantly reduced in patients with cardiac amyloidosis compared with controls (−15.3 ± 4.1% vs. −21.2 ± 5.4%, p < 0.001). Compared with conventional RV strain, the investigational biventricular tracking approach yielded more negative global RV strain values in both patients with amyloidosis (−15.3 ± 4.1% vs. −13.8 ± 4.8%, p = 0.003) and controls (−21.2 ± 5.4% vs. −17.4 ± 5.8%, p < 0.001). The greatest differences were observed at the apical RV segment. Bland–Altman analysis demonstrated a mean bias of −2.64 percentage points with 95% limits of agreement from −8.41 to +3.12 percentage points. A significant regional deformation pattern along the investigational tracking contour was observed in patients with cardiac amyloidosis (p < 0.001), whereas no significant regional variation was observed in controls. BVS correlated strongly with LV global longitudinal strain (r = 0.83 in amyloidosis; r = 0.58 in controls; r = 0.84 overall; all p < 0.001). Inter- and intra-observer reproducibility of investigational RV free-wall strain was excellent (ICC 0.976 and 0.985, respectively). Conclusions: The investigational biventricular tracking approach is a feasible and highly reproducible method for assessing ventricular longitudinal deformation using a single continuous contour. It provides complementary information while remaining an exploratory investigational technique. Further studies are required to validate its anatomical specificity, clinical applicability, and prognostic value.
Full article
(This article belongs to the Section Cardiac and Cardiovascular Systems)
►▼
Show Figures

Graphical abstract

Journal Menu
► ▼ Journal Menu-
- Clinics and Practice Home
- Aims & Scope
- Editorial Board
- Topical Advisory Panel
- Instructions for Authors
- Special Issues
- Topics
- Sections
- Article Processing Charge
- Indexing & Archiving
- Editor’s Choice Articles
- Most Cited & Viewed
- Journal Statistics
- Journal History
- Journal Awards
- Conferences
- Editorial Office
Journal Browser
► ▼ Journal BrowserHighly Accessed Articles
Latest Books
E-Mail Alert
News
Topics
Topic in
JCM, Medicina, Prosthesis, IJMS, Clinics and Practice
Innovations in Plastic Surgery and Regenerative Medicine—2nd Edition
Topic Editors: Francesco D’Andrea, Jean Paul Meningaud, Barbara Hersant, Simone La PadulaDeadline: 30 November 2026
Topic in
Brain Sciences, Children, Foods, Geriatrics, Nutrients, Clinics and Practice, Dietetics, JGG
Lifestyle, Health and Mental Well-Being Across the Lifespan
Topic Editors: Tonia Vassilakou, Rena I. Kosti, Maria G. GrammatikopoulouDeadline: 31 December 2026
Topic in
Biomechanics, Clinics and Practice, JFMK, Medicina, Sports
Biomechanics, Rehabilitation, and Metabolic Health: The Role of Physical Activity in Managing Chronic Conditions
Topic Editors: Jan Bilski, Nicola Luigi BragazziDeadline: 28 February 2027
Topic in
Biomedicines, Clinics and Practice, Diseases, JCM, Pathophysiology, Diagnostics
Evolving Insights into Pathophysiology, Diagnosis, Therapy, and Prognosis in Acute Respiratory Distress Syndrome (ARDS): From Bench to Bedside—Third Edition
Topic Editors: Denise Battaglini, Patricia Rieken Macêdo Rocco, Raffaele MerolaDeadline: 31 March 2027
Conferences
Special Issues
Special Issue in
Clinics and Practice
Clinical Outcome Research in the Head and Neck: 2nd Edition
Guest Editors: Athanassios A. Kyrgidis, Ioannis TilaveridisDeadline: 31 October 2026
Special Issue in
Clinics and Practice
Emergency and Disaster Medicine: Preparedness, Response, and Resilience in Health Systems
Guest Editor: Ulrich SackDeadline: 31 October 2026
Special Issue in
Clinics and Practice
Translational Pharmacogenomics in Clinical Practice: Advancing Precision Drug Therapy
Guest Editor: Andrea GažováDeadline: 31 October 2026
Special Issue in
Clinics and Practice
At-Risk Mental States: Clinical Presentation and Psychopathological Comorbidities
Guest Editor: Michele RibolsiDeadline: 30 November 2026