Skip to Content
  • Tracked for
    Impact Factor
  • 25 days
    Submission to First Decision
  • 5 days
    Acceptance to Publication

Emergency Care and Medicine

Emergency Care and Medicine is an international, peer-reviewed, open access journal on advancements and developments in emergency medical services, emergency medicine, acute internal medicine, and acute care surgery practice, theory, nursing, training, and education published quarterly online by MDPI.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (141)

  • Article
  • Open Access

Background/Objectives: The VA Emergency Medicine Addiction Hotline (VEMAH) is a real-time telehealth addiction consult service for Veterans Health Administration (VHA) providers in acute-care settings. Methods: This descriptive report used the program’s case tracker and VHA Emergency Department Opioid Safety Initiative (ED OSI) dashboard data. VEMAH launched in May 2023 as an eight-facility pilot in Veterans Integrated Service Network 22 (VISN 22) and expanded to 17 VHA sites; all analyses are limited to the eight pilot sites. Results: Over 38 months, the eight VISN 22 sites recorded 2154 encounters (not unique patients), including e-consults, direct patient tele-care, care coordination, proactive tele-outreach, and provider education. Common indications were opioid-related (41.9%) and alcohol-related (34.1%) concerns; pain-related concerns accounted for 11.3%. Most encounters (64.8%) were initiated by VEMAH clinicians. ED OSI naloxone and buprenorphine scores rose in VISN 22 after launch, but slopes were similar to or shallower than elsewhere in VHA, and the naloxone increase came in steps at launch and at the Phoenix site. Conclusions: In the eight-facility pilot, VEMAH brought real-time addiction expertise to acute-care clinicians, most often through proactive outreach by VEMAH clinicians. The service has since expanded within VHA; this report covers the pilot only, and effects and feasibility were not evaluated.

Emerg. Care Med.

18 November 2026

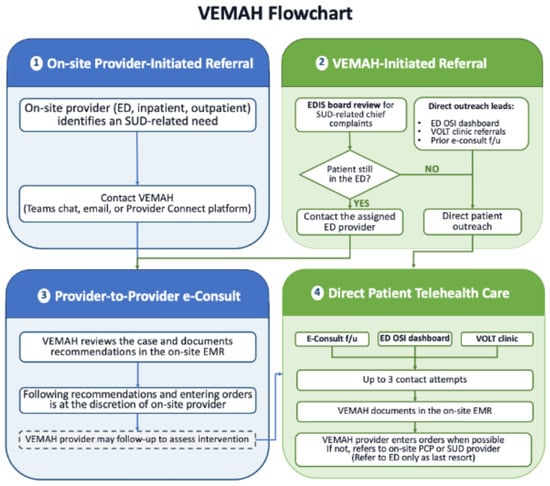
VEMAH Flowchart. Note: In provider-to-provider e-consults (3), the on-site clinician decides whether to follow recommendations and enters orders. In direct patient telehealth care (4), the VEMAH provider enters orders when possible.
  • Review
  • Open Access

Unexpected postoperative impairment of consciousness may reflect residual anesthesia, encephalopathy, brain injury or nonconvulsive seizures. To appraise bilateral bispectral index (BIS) monitoring and its potential role in postoperative neurological surveillance. This critical narrative review used a focused search of four bibliographic databases and the manual selection of contextual literature. Direct bilateral BIS evidence was distinguished from sedation studies and other EEG technologies. A retrospective series of 15 patients with established nonconvulsive status epilepticus (NCSE) described potentially useful follow-up patterns. A comparison in 48 patients undergoing presurgical epilepsy assessment did not demonstrate reliable seizure detection against 40-channel EEG. Neither direct cohort studied postoperative ICU seizure surveillance. Evidence from sedation, ischemia and prognosis addresses different clinical questions. When already available, bilateral BIS may prompt signal checks and neurological reassessment. Suspected seizures require diagnostic EEG irrespective of the BIS display. The proposed postoperative application requires prospective validation.

Emerg. Care Med.

18 November 2026

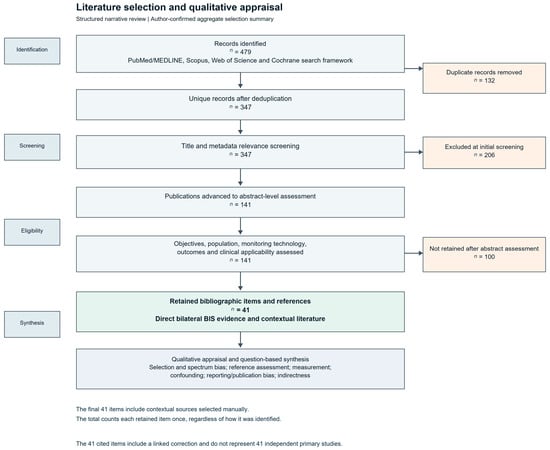
Aggregate literature selection for the critical narrative review. The recorded counts were 479 database records, 132 duplicates removed, 347 unique records, 206 title or metadata exclusions, 141 abstracts assessed, 100 further exclusions and 41 retained bibliographic items. The final count includes manually selected contextual sources, counted once per item. The flow does not allocate the retained items by retrieval route. The 41 items include a linked correction and do not represent 41 independent primary studies.
  • Systematic Review
  • Open Access

Background: Peripheral norepinephrine enables timely vasopressor initiation, but local safety remains uncertain. This rapid review mapped administration practices and local adverse events in critically ill adults. Methods: Following Joanna Briggs Institute and Cochrane rapid review guidance and PRISMA 2020 (OSF: 10.17605/OSF.IO/6VH9E), PubMed, MEDLINE Complete and CINAHL Complete were searched through 22 August 2026 (PubMed re-run with corrected syntax within this limit). Included syntheses were citation-searched. Short peripheral intravenous and midline catheters were analysed separately; peripherally inserted central catheters were classified as central access. Results: Thirty-nine sources were included (27 primary studies, seven syntheses, five normative documents); three reports were unavailable. In 14 norepinephrine-specific reports using short peripheral catheters, source-defined extravasation or infiltration occurred in 0–5.6% of patients or infusions, and with midline catheters in one of 472 episodes; composite local events were analysed separately. Serious injury was inconsistently assessed; one fasciotomy occurred among 3734 patients in a mixed-agent cohort. Confidence was low to very low for all outcomes. Conclusions: Observational evidence suggests that peripheral norepinephrine is feasible in selected critically ill adults under structured monitoring and extravasation-response protocols, with infrequent, mostly minor events, but does not establish comparative safety or universal concentration, dose or duration limits.

Emerg. Care Med.

5 November 2026

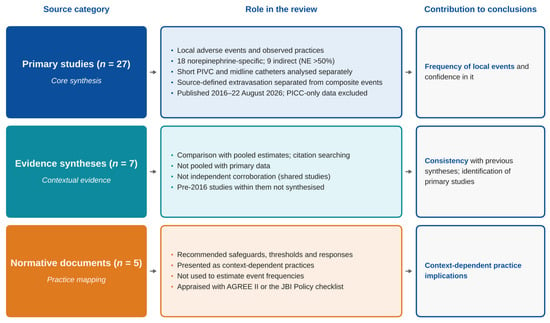
Structure of the review: role of each source category and its contribution to the conclusions. NE, norepinephrine; PICC, peripherally inserted central catheter; PIVC, peripheral intravenous catheter.
  • Review
  • Open Access

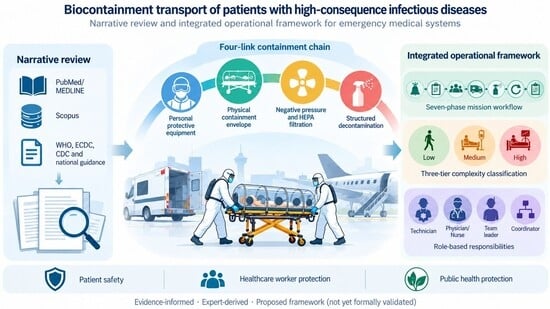
Background/Objectives: The transport of patients with high-consequence infectious diseases (HCIDs) links biosafety science and emergency medicine. The 2026 Bundibugyo virus disease epidemic and the multinational Andes virus outbreak associated with an expedition cruise ship have renewed attention on how such patients are moved safely between the community, hospitals and high-level isolation units. This narrative review synthesises the international literature on biocontainment transport and integrates it into an operational framework for emergency medical systems. Methods: A structured search of PubMed/MEDLINE and Scopus (to 10 October 2026), complemented by guidance from the World Health Organization, the European Centre for Disease Prevention and Control, the US Centers for Disease Control and Prevention and national authorities, was conducted, and the review was planned and written using the SANRA quality criteria. Evidence was organised across seven operational domains and combined with the operational experience of the Public Health Unit of the Italian Red Cross (CRI). Results: Of 2432 records identified, 1485 unique records were screened. The literature is dominated by aeromedical case reports, technical evaluations and expert consensus, with few comparative studies. Recurrent findings concern device integrity and air quality within transport isolators, the risk of self-contamination during doffing, heat strain and communication limits imposed by personal protective equipment, decontamination of vehicles and isolators, the maintenance of team readiness during periods of low activity, and the psychological burden on patients and staff. These findings are integrated into a framework comprising a four-link containment chain, a seven-phase operational workflow, a three-tier complexity classification and a role-based responsibility matrix. Conclusions: Biocontainment transport is better understood as an integrated emergency system than as a device-centred intervention. The proposed framework is a structured, consensus-based reference for planning, training and quality assurance; its components require prospective evaluation.

Emerg. Care Med.

1 November 2026

Article thumbnail image

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Emerg. Care Med. - ISSN 2813-7914