Skip to Content
You are currently on the new version of our website. Access the old version .
  • 3.7
    CiteScore
  • 30 days
    Submission to First Decision
  • 12 days
    Acceptance to Publication

Journal of Market Access & Health Policy

Journal of Market Access & Health Policy (JMAHP) is an international, peer-reviewed, open access journal that covers all different subdisciplines of ‘market access’ from economic, technical, scientific, sociological, psychological and policy perspectives, published quarterly online. It is the official journal of the Market Access Society (MAS). Society members receive discounts on the APCs.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (389)

  • Article
  • Open Access

Per-Patient Medical Costs of Hemodialysis and Peritoneal Dialysis in Japan

  • Akina Takami,
  • Gen Terashima and
  • Yoshitaka Ishibashi
  • + 2 authors

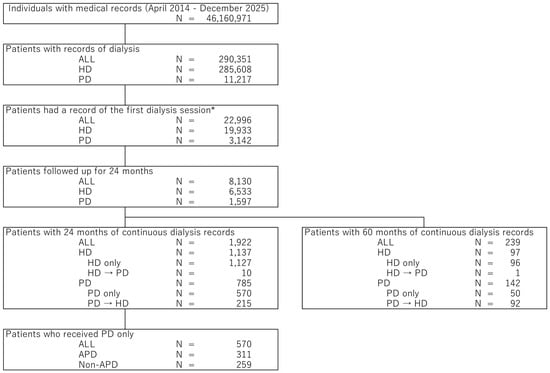
Introduction: Dialysis therapy imposes a substantial economic burden, and data on per-patient medical costs between hemodialysis (HD) and peritoneal dialysis (PD) in Japan based on large-scale databases are limited. Methods: This retrospective cohort study used the JMDC medical institution database (April 2014 to December 2025). Patients with continuous monthly dialysis records for 24 months (n = 1922; HD: 1137, PD: 785) and 60 months (n = 239) were included. Per-patient medical costs were compared between the HD and PD groups. Results: In patients with 24-month dialysis records, monthly medical costs (mean ± SD) were 441,421 ± 136,209 JPY for the HD-only group and 378,038 ± 157,118 JPY for the PD-only group. Year 2 medical costs were 4,992,931 ± 1,718,757 JPY and 4,078,469 ± 2,009,366 JPY, respectively, with PD costs being approximately 18% lower than HD. Among PD patients, those in the non-APD group had lower monthly costs (319,731 JPY) compared with those who used APD for all 24 months (451,702 JPY). Conclusions: Per-patient medical costs for PD patients in Japan were lower than for HD patients. These findings show lower per-patient medical costs associated with PD and complement macro-level analyses using national databases.

Patient flow. There was an overlap between patients followed for 24 months and those followed for 60 months. APD, automated peritoneal dialysis; HD, hemodialysis; PD, peritoneal dialysis. * Patients had a record of the first dialysis session in the database in the same month or the following month as K612 (for HD) or K635-3 and K635-4 (for PD).
  • Article
  • Open Access

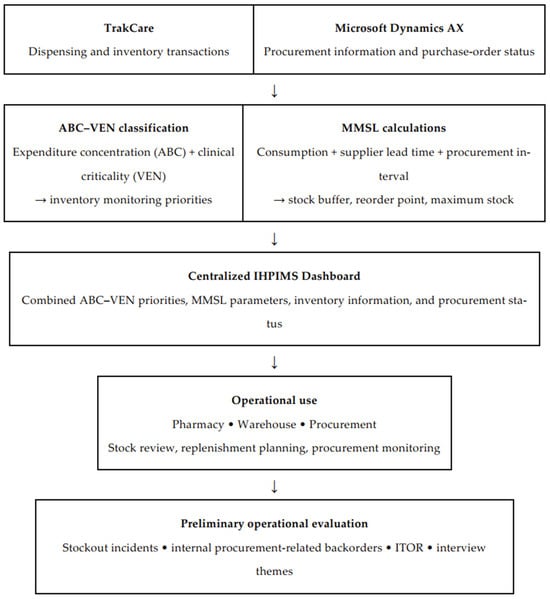
Effective pharmaceutical inventory management supports drug availability, financial sustainability, and patient safety. This study presents preliminary operational evaluation of an Integrated Hospital Pharmacy Inventory Management System (IHPIMS) combining Always Better Control–Vital, Essential, Nonessential (ABC–VEN) analysis and Minimum–Maximum Stock Level (MMSL) methods. A mixed-methods study was conducted at a private Indonesian hospital to compare stockout incidents and inventory turnover ratio (ITOR) during January–June 2023 with the first complete post-implementation month, November 2023. Qualitative data were collected through semi-structured interviews and analyzed using thematic content analysis. Twelve stockout incidents were recorded in November, compared with a pre-implementation monthly average of 28 incidents. No backorders attributed to internal procurement delays were observed in the evaluation period. ITOR decreased from 7 to 6, corresponding to approximately 60 days of inventory during the post-implementation month. IHPIMS was operationally feasible and provided a centralized platform for inventory monitoring and procurement coordination. However, because multiple operational changes occurred concurrently and only one post-implementation month was evaluated, these findings should be interpreted as preliminary operational observations rather than evidence of causal effectiveness. Longer-term evaluation is required to determine whether these findings are sustained over time.

Operational Integration of IHPIMS.
  • Article
  • Open Access

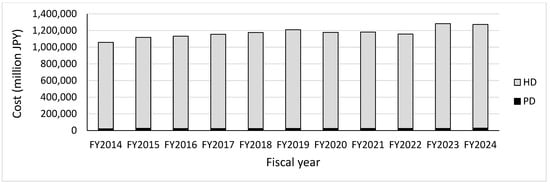
Introduction: Although the high cost of dialysis therapy can be an economic burden, peritoneal dialysis (PD) accounts for approximately 3% of the dialysis population. Studies comparing medical costs of PD and hemodialysis (HD) in Japan are limited. We investigated medical expenditures of PD and HD using the National Database (NDB) Open Data to clarify the current status of dialysis modality-specific medical expenditures in Japan. Methods: This was a descriptive analysis of aggregate data from the NDB Open Data for fiscal years 2014 to 2024 (April 2014 to March 2025). Dialysis-related items were extracted from the dataset. In this study, medical expenditures related to PD and HD were aggregated. Results: Total dialysis therapy expenditures showed an increasing trend from 1,057,950 million JPY in fiscal year 2014 to 1,209,499 million JPY in fiscal year 2019. Although a slight decline was observed thereafter, total expenditures reached 1,272,637 million JPY in fiscal year 2024. PD-related medical expenditures consistently accounted for approximately 2% of total dialysis therapy expenditures throughout the study period; HD-related expenditures comprised the majority. Conclusions: This study found that total dialysis therapy expenditures in Japan reached approximately 1.273 trillion JPY in fiscal year 2024, with HD-related medical expenditures accounting for the majority.

Changes in dialysis therapy expenditures by fiscal year. FY, fiscal year; HD, hemodialysis; PD, peritoneal dialysis.
  • Article
  • Open Access

Introduction: Medicine prices change over the product life cycle, especially around loss of exclusivity (LoE), yet economic evaluations often assume constant prices, which may bias cost-effectiveness and budget impact estimates. Methods: We developed and internally validated a forecasting approach for Dutch medicine price trajectories for use in cost-effectiveness analyses. Using monthly Farminform sales data (from 2000 onwards) for 384 Anatomical Therapeutic Chemical (ATC) codes meeting the inclusion criteria (>5 years of data, <6 months missing, data after 2017), we derived inflation-adjusted mean prices per defined daily dose. A stacked machine learning ensemble, combining XGBoost, Random Forest, Bayesian additive regression trees, a regularised generalised linear model, and LightGBM gradient boosting, was tuned by ATC-grouped cross-validation to minimise root mean squared error (RMSE), with weights estimated by non-negative penalised regression. Results: Predictors included therapeutic class and subgroup, market entry period, initial price, revenue group, time on market, LoE status and time since LoE, inflation, and competitor availability. On 103 held-out time series, the six-model ensemble achieved an RMSE of 0.199. Predicted trajectories were highly accurate for 26% of products (within ±5% of observed prices) and of medium accuracy for 47% (overall trend captured; most observations within ±12.5%). Poor accuracy (27%) mainly reflected abrupt price shifts linked to policy changes, reimbursement decisions, or pricing negotiations. Conclusions: Forecasting life-cycle medicine price trajectories is feasible for most products and can support more realistic economic evaluations and reimbursement deliberations in the Netherlands. Remaining challenges include anticipating policy-driven discontinuities and improving interpretability of machine-learning-based forecasts.

Method for calculating the relative price per DDD of medicine. DDD: defined daily dose, ATC: Anatomical Therapeutic Chemical, inf: inflation.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
J. Mark. Access Health Policy - ISSN 2001-6689