Decoding CAPA: A Comparative Study of AspICU, ISHAM, and EORTC Criteria in Critical COVID-19 Patients Requiring Mechanical Ventilation


Abstract
1. Introduction
2. Methods
2.1. Study Design
2.2. Study Population
2.3. Diagnosis of CAPA
2.4. Statistical Analysis: No Multivariate Analysis or Correction for Multiple Comparisons Was Performed, Given the Exploratory and Descriptive Nature of This Study
3. Results
3.1. Study Population
3.2. Respiratory Management and Outcomes
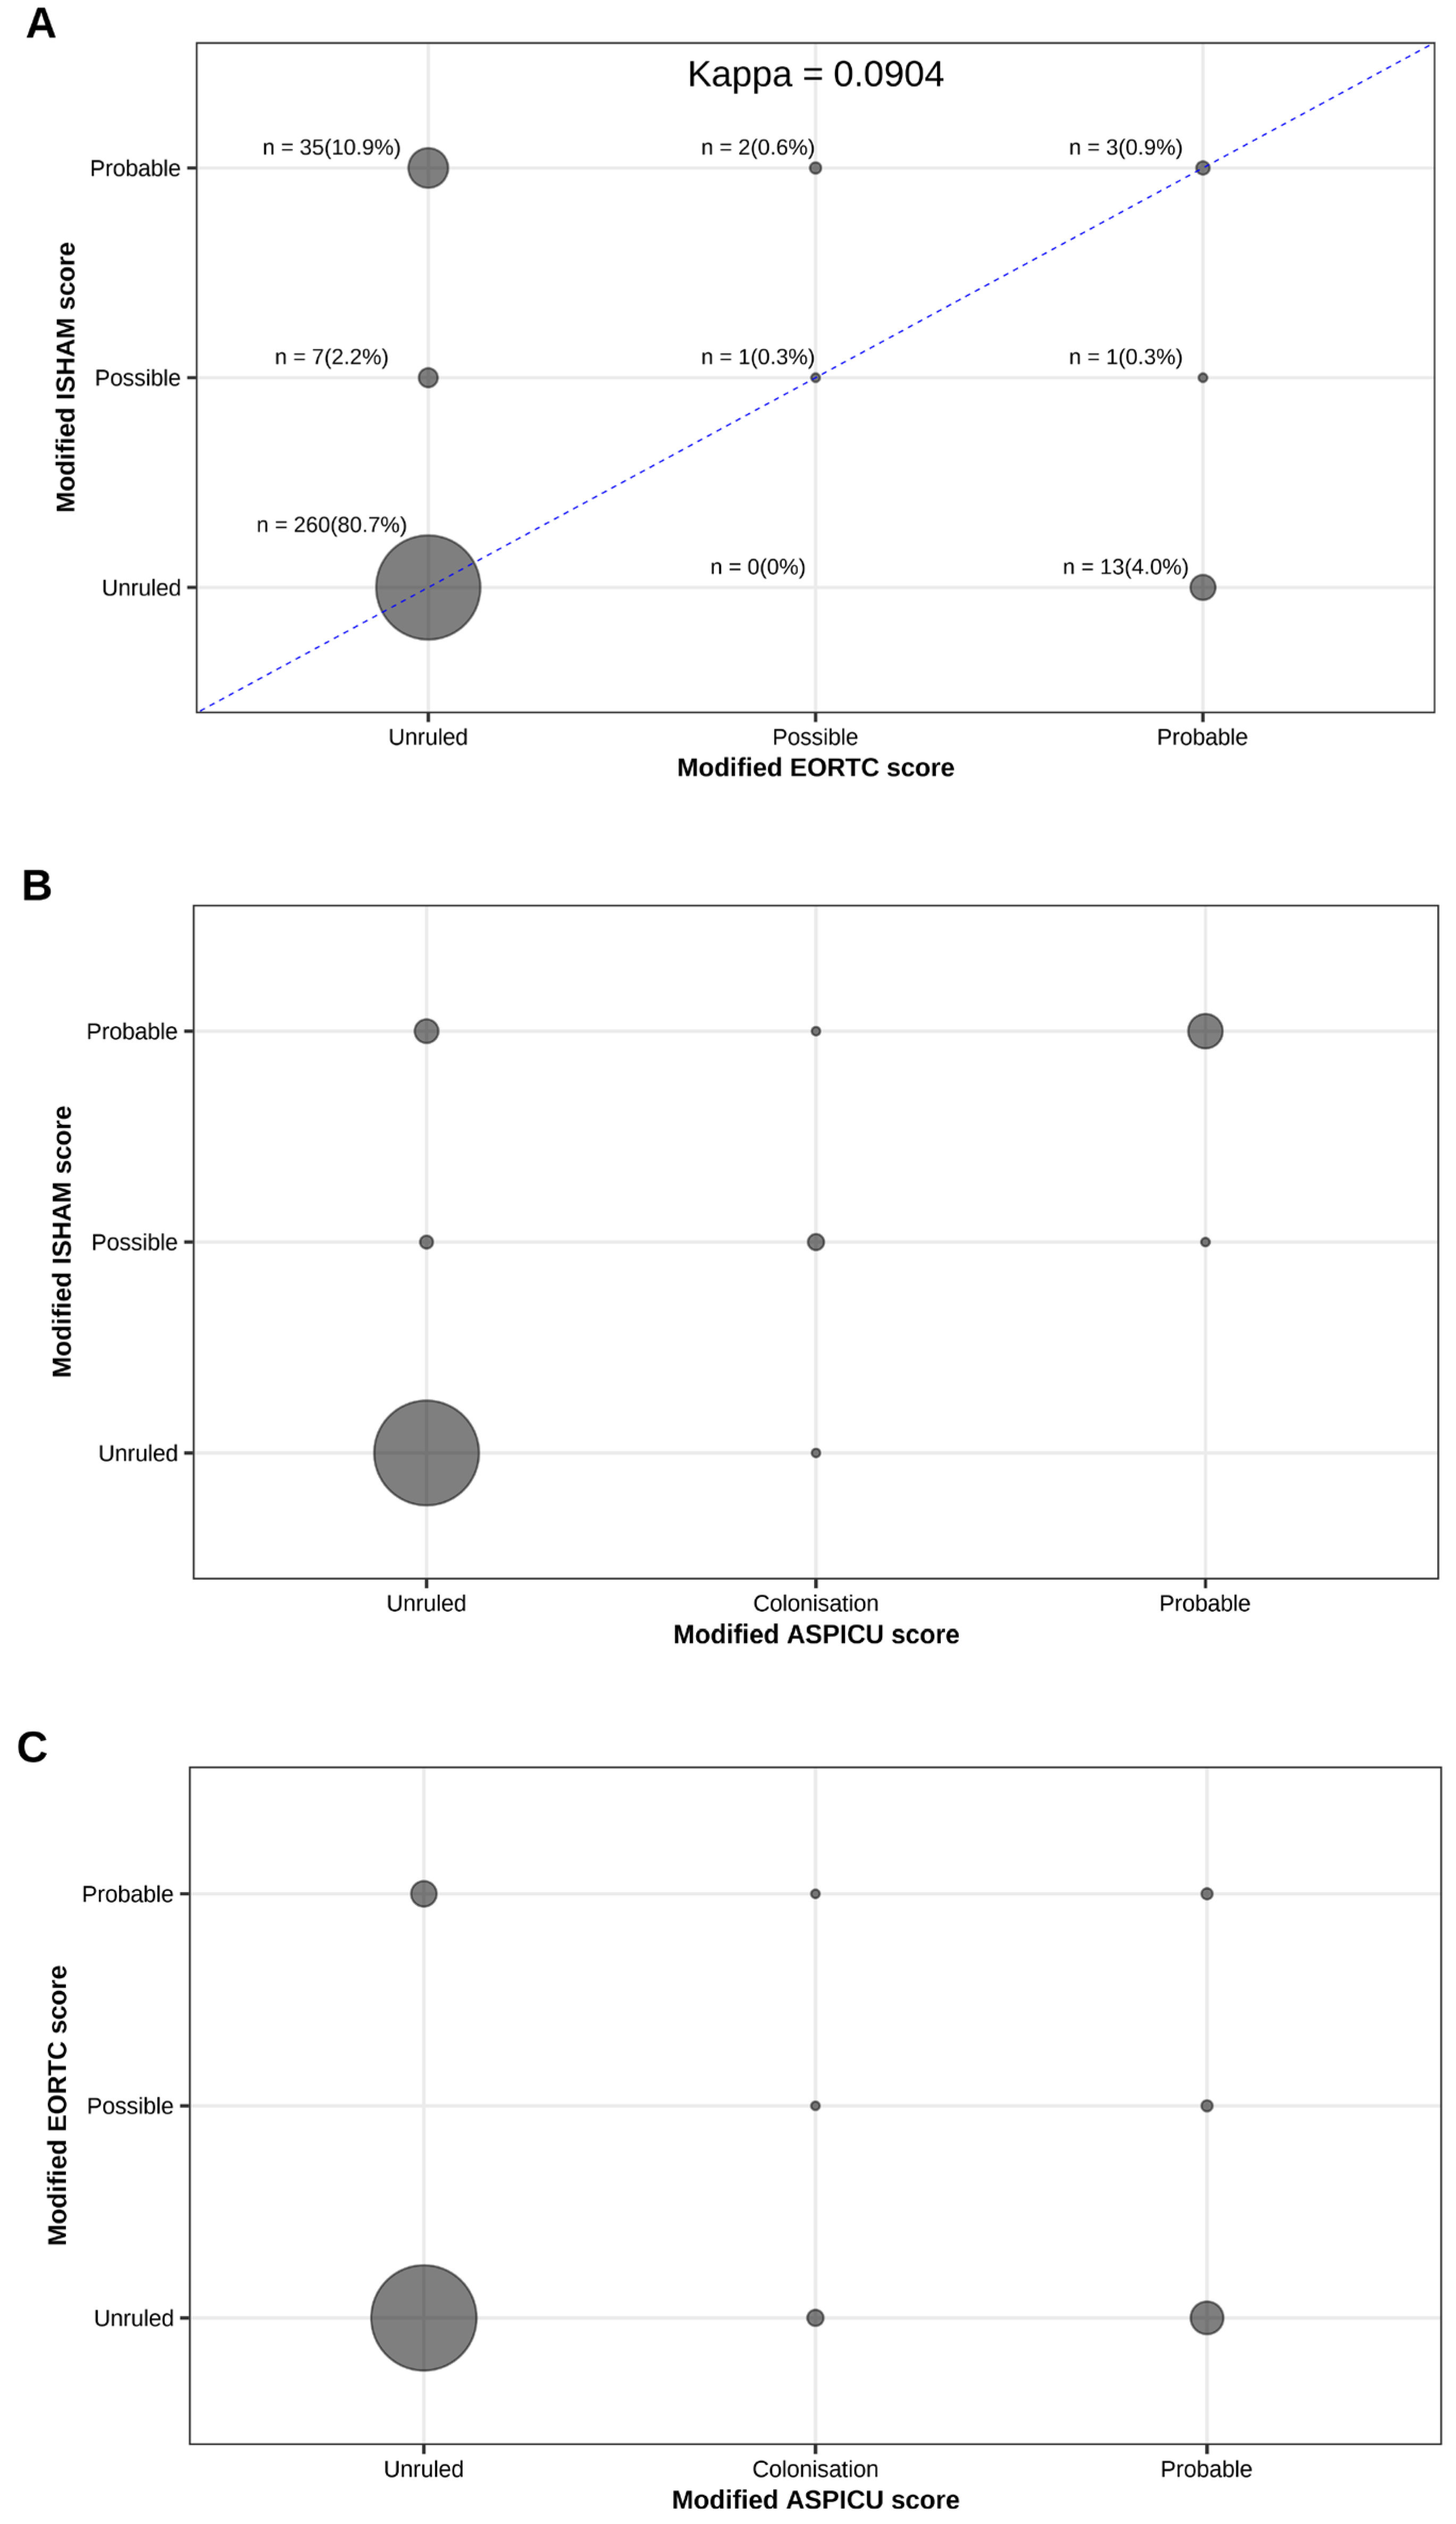
3.3. CAPA Classification According to Diagnostic Criteria
3.4. Mortality According to CAPA Classification
3.5. Evolution Across COVID-19 Waves
4. Discussion
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
References
- Grasselli, G.; Pesenti, A.; Cecconi, M. Critical Care Utilization for the COVID-19 Outbreak in Lombardy, Italy: Early Experience and Forecast During an Emergency Response. JAMA 2020, 323, 1545–1546. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, S.F.; Wu, A.Y.; Lee, S.S.; Huang, Y.S.; Lee, C.Y.; Yang, T.L.; Wang, H.W.; Chen, H.J.; Chen, Y.C.; Ho, T.S.; et al. COVID-19 associated mold infections: Review of COVID-19 associated pulmonary aspergillosis and mucormycosis. J. Microbiol. Immunol. Infect. 2023, 56, 442–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rouzé, A.; Lemaitre, E.; Martin-Loeches, I.; Povoa, P.; Diaz, E.; Nyga, R.; Torres, A.; Metzelard, M.; Cheyron, D.D.; Lambiotte, F.; et al. Invasive pulmonary aspergillosis among intubated patients with SARS-CoV-2 or influenza pneumonia: A European multicenter comparative cohort study. Crit. Care 2022, 26, 11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schauwvlieghe, A.F.; Rijnders, B.J.; Philips, N.; Verwijs, R.; Vanderbeke, L.; Van Tienen, C.; Lagrou, K.; Verweij, P.E.; Van de Veerdonk, F.L.; Gommers, D.; et al. Invasive aspergillosis in patients admitted to the intensive care unit with severe influenza: A retrospective cohort study. Lancet Respir. Med. 2018, 6, 782–792. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gangneux, J.P.; Dannaoui, E.; Fekkar, A.; Luyt, C.E.; Botterel, F.; De Prost, N.; Tadié, J.M.; Reizine, F.; Houzé, S.; Timsit, J.-F.; et al. Fungal infections in mechanically ventilated patients with COVID-19 during the first wave: The French multicentre MYCOVID study. Lancet Respir. Med. 2022, 10, 180–190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prattes, J.; Wauters, J.; Giacobbe, D.R.; Salmanton-García, J.; Maertens, J.; Bourgeois, M.; Reynders, M.; Rutsaert, L.; Van Regenmortel, N.; Lormans, P.; et al. Risk factors and outcome of pulmonary aspergillosis in critically ill coronavirus disease 2019 patients-a multinational observational study by the European Confederation of Medical Mycology. Clin. Microbiol. Infect. 2022, 28, 580–587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Apostolopoulou, A.; Esquer Garrigos, Z.; Vijayvargiya, P.; Lerner, A.H.; Farmakiotis, D. Invasive Pulmonary Aspergillosis in Patients with SARS-CoV-2 Infection: A Systematic Review of the Literature. Diagnostics 2020, 10, 807. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verweij, P.E.; Rijnders, B.J.; Brüggemann, R.J.; Azoulay, E.; Bassetti, M.; Blot, S.; Calandra, T.; Clancy, C.J.; Cornely, O.A.; Chiller, T.; et al. Review of influenza-associated pulmonary aspergillosis in ICU patients and proposal for a case definition: An expert opinion. Intensive Care Med. 2020, 46, 1524–1535. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haydour, Q.; Hage, C.A.; Carmona, E.M.; Epelbaum, O.; Evans, S.E.; Gabe, L.M.; Knox, K.S.; Kolls, J.K.; Wengenack, N.L.; Prokop, L.J.; et al. Diagnosis of Fungal Infections. A Systematic Review and Meta-Analysis Supporting American Thoracic Society Practice Guideline. Ann. Am. Thorac. Soc. 2019, 16, 1179–1188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Misset, B.; Piagnerelli, M.; Hoste, E.; Dardenne, N.; Grimaldi, D.; Michaux, I.; De Waele, E.; Dumoulin, A.; Jorens, P.G.; van der Hauwaert, E.; et al. Convalescent plasma for Covid-19–induced ARDS in mechanically ventilated patients. N. Engl. J. Med. 2023, 389, 1590–1600. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blot, S.I.; Taccone, F.S.; Van den Abeele, A.M.; Bulpa, P.; Meersseman, W.; Brusselaers, N.; Dimopoulos, G.; Paiva, J.A.; Misset, B.; Rello, J.; et al. A clinical algorithm to diagnose invasive pulmonary aspergillosis in critically ill patients. Am. J. Respir. Crit. Care Med. 2012, 186, 56–64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dellière, S.; Dudoignon, E.; Voicu, S.; Collet, M.; Fodil, S.; Plaud, B.; Chousterman, B.; Bretagne, S.; Azoulay, E.; Mebazaa, A.; et al. Combination of Mycological Criteria: A Better Surrogate to Identify COVID-19-Associated Pulmonary Aspergillosis Patients and Evaluate Prognosis? J. Clin. Microbiol. 2022, 60, e0216921. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fortarezza, F.; Boscolo, A.; Pezzuto, F.; Lunardi, F.; Acosta, M.J.; Giraudo, C.; Del Vecchio, C.; Sella, N.; Tiberio, I.; Godi, I.; et al. Proven COVID-19-associated pulmonary aspergillosis in patients with severe respiratory failure. Mycoses 2021, 64, 1223–1229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koehler, P.; Bassetti, M.; Chakrabarti, A.; Chen, S.C.; Colombo, A.L.; Hoenigl, M.; Klimko, N.; Lass-Flörl, C.; Oladele, R.O.; Vinh, D.C.; et al. Defining and managing COVID-19-associated pulmonary aspergillosis: The 2020 ECMM/ISHAM consensus criteria for research and clinical guidance. Lancet Infect. Dis. 2021, 21, e149–e162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bassetti, M.; Azoulay, E.; Kullberg, B.J.; Ruhnke, M.; Shoham, S.; Vazquez, J.; Giacobbe, D.R.; Calandra, T. EORTC/MSGERC Definitions of Invasive Fungal Diseases: Summary of Activities of the Intensive Care Unit Working Group. Clin. Infect. Dis. 2021, 72, S121–S127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Horby, P.; Lim, W.S.; Emberson, J.R.; Mafham, M.; Bell, J.L.; Linsell, L.; Staplin, N.; Brightling, C.; Ustianowski, A.; RECOVERY Collaborative Group; et al. Dexamethasone in Hospitalized Patients with Covid-19. N. Engl. J. Med. 2021, 384, 693–704. [Google Scholar] [PubMed]


| Group 0—No suspected aspergillosis: No mycological analysis was performed during ICU stay, as patients remained stable or their respiratory condition improved throughout their course. Group 1—Aspergillus colonization: Defined by a positive respiratory Aspergillus culture in a patient with no signs of respiratory, hemodynamic deterioration, or persisting fever. Group 2—Possible aspergillosis: Defined by the onset of respiratory or hemodynamic worsening and/or persistent fever prompting a mycological investigation (BAL, tracheal aspirate, etc.), regardless of whether the result was positive or negative. Group 3—Probable aspergillosis: Patients presenting with clinical deterioration and at least one positive mycological test (culture or galactomannan) consistent with invasive fungal disease. Group 4—Proven aspergillosis: Confirmed by anatomopathological evidence of tissue invasion by Aspergillus species |
| Characteristic | Overall N = 328 | 1, N = 25 | 2, N = 105 | 3, N = 135 | 4, N = 63 |
|---|---|---|---|---|---|
| Age | 63.0 (54.8, 71.0) | 60.0 (56.0, 66.0) | 66.0 (59.0, 73.0) | 64.0 (57.0, 70.0) | 58.0 (50.0, 66.5) |
| Females | 114/328 (34.8%) | 10/25 (40.0%) | 36/105 (34.3%) | 43/135 (31.9%) | 25/63 (39.7%) |
| Males | 214/328 (65.2%) | 15/25 (60.0%) | 69/105 (65.7%) | 92/135 (68.1%) | 38/63 (60.3%) |
| BMI | 30.1 (26.8, 34.5) | 30.4 (28.7, 33.3) | 29.8 (26.7, 34.3) | 30.3 (26.5, 33.5) | 31.0 (27.0, 37.0) |
| Comorbidities | |||||
| Hypertension | 188/328 (57.3%) | 19/25 (76.0%) | 66/105 (62.9%) | 70/135 (51.9%) | 33/63 (52.4%) |
| Diabetes | 132/328 (40.2%) | 10/25 (40.0%) | 46/105 (43.8%) | 47/135 (34.8%) | 29/63 (46.0%) |
| Ischemic heart disease | 41/328 (12.5%) | 2/25 (8.0%) | 10/105 (9.5%) | 22/135 (16.3%) | 7/63 (11.1%) |
| Immunosuppression | 42/328 (12.8%) | 2/25 (8.0%) | 11/105 (10.5%) | 13/135 (9.6%) | 16/63 (25.4%) |
| Chronic kidney failure | 42/328 (12.8%) | 2/25 (8.0%) | 12/105 (11.4%) | 20/135 (14.8%) | 8/63 (12.7%) |
| COPD | 34/328 (10.4%) | 2/25 (8.0%) | 17/105 (16.2%) | 13/135 (9.6%) | 2/63 (3.2%) |
| Active cancer (<2 years) | 22/328 (6.7%) | 0/25 (0.0%) | 11/105 (10.5%) | 9/135 (6.7%) | 2/63 (3.2%) |
| SOFA score at ICU admission | 5.0 (3.0, 7.0) | 6.0 (4.0, 7.0) | 5.0 (4.0, 8.0) | 4.0 (3.0, 7.0) | 5.0 (4.0, 7.0) |
| APACHE score | 13.0 (10.0, 17.0) | 13.0 (10.0, 19.0) | 15.0 (11.0, 18.0) | 12.0 (9.0, 16.0) | 10.0 (9.0, 14.0) |
| Characteristic | Overall N = 328 | 1, N = 25 | 2, N = 105 | 3, N = 135 | 4, N = 63 |
|---|---|---|---|---|---|
| Mechanical ventilation duration (days) | 12.0 (6.0, 20.0) | 10.0 (6.0, 14.0) | 10.0 (6.0, 16.0) | 15.0 (8.0, 24.5) | 13.0 (6.0, 21.0) |
| Sedation duration (days) | 11.0 (5.0, 16.0) | 7.0 (4.0, 12.0) | 8.5 (5.0, 13.0) | 12.0 (7.0, 17.8) | 11.5 (6.0, 19.3) |
| Prone position (session) | 2.0 (1.0, 3.0) | 2.0 (1.0, 2.0) | 1.0 (1.0, 3.0) | 2.0 (1.0, 3.0) | 2.5 (1.0, 6.0) |
| Days under curare use | 8.0 (4.0, 14.0) | 5.0 (3.0, 10.0) | 6.0 (2.0, 10.0) | 10.0 (5.0, 15.0) | 11.0 (5.8, 18.0) |
| ECMO support | 51/328 (15.5%) | 6/25 (24.0%) | 14/105 (13.3%) | 24/135 (17.8%) | 7/63 (11.1%) |
| ECMO days to weaning (days) | 13.0 (8.0, 20.5) | 10.5 (7.3, 18.3) | 9.5 (8.0, 12.8) | 19.0 (12.0, 28.0) | 12.0 (6.0, 25.0) |
| Use of dexamethasone | 290/327 (88.7%) | 0/25 (0.0%) | 99/105 (94.3%) | 131/134 (97.8%) | 60/63 (95.2%) |
| Methylprednisolone | 36/326 (11.0%) | 0/25 (0.0%) | 1/105 (1.0%) | 21/133 (15.8%) | 14/63 (22.2%) |
| Hydrocortisone | 22/327 (6.7%) | 21/25 (84.0%) | 1/105 (1.0%) | 0/135 (0.0%) | 0/62 (0.0%) |
| Azithromycin | 7/327 (2.1%) | 2/25 (8.0%) | 2/105 (1.9%) | 2/135 (1.5%) | 1/62 (1.6%) |
| Remdesivir use | 6/326 (1.8%) | 0/25 (0.0%) | 6/105 (5.7%) | 0/134 (0.0%) | 0/62 (0.0%) |
| Convalescent plasma | 35/326 (10.7%) | 0/25 (0.0%) | 22/105 (21.0%) | 13/135 (9.6%) | 0/61 (0.0%) |
| Characteristic | Overall N = 328 | 1, N = 25 | 2, N = 105 | 3, N = 135 | 4, N = 63 |
|---|---|---|---|---|---|
| Previous COVID symptoms (days) | 8.0 (6.0, 10.0) | 9.0 (5.0, 12.0) | 8.0 (6.3, 10.0) | 8.0 (7.0, 10.0) | 8.0 (6.0, 10.0) |
| ICU ospitalization from symptoms (days) | 1.0 (0.0, 3.0) | 0.0 (0.0, 2.0) | 1.0 (0.0, 2.0) | 1.0 (0.0, 3.0) | 1.0 (0.0, 4.0) |
| ICU LOS (days) | 14.0 (8.0, 23.0) | 14.0 (10.0, 20.0) | 12.0 (7.0, 19.0) | 16.0 (10.0, 26.8) | 13.0 (7.5, 23.5) |
| Hospital LOS (days) | 21.0 (13.5, 33.5) | 21.0 (14.0, 29.0) | 19.0 (11.0, 27.0) | 23.0 (15.0, 36.8) | 23.5 (13.8, 40.3) |
| ICU survival | 192/328 (58.5%) | 17/25 (68.0%) | 56/105 (53.3%) | 88/135 (65.2%) | 31/63 (49.2%) |
| Survival at day 28 | 198/327 (60.6%) | 17/25 (68.0%) | 57/105 (54.3%) | 90/134 (67.2%) | 34/63 (54.0%) |
| Hospital survival | 183/328 (55.8%) | 17/25 (68.0%) | 55/105 (52.4%) | 81/135 (60.0%) | 30/63 (47.6%) |
| Characteristic | Overall N = 218 | 1, N = 25 | 2, N = 105 | 3, N = 135 | 4, N = 63 |
|---|---|---|---|---|---|
| Positive galactomannan | 32/218 (14.7%) | 1/12 (8.3%) | 6/75 (8.0%) | 15/85 (17.6%) | 10/46 (21.7%) |
| Galactomannan result | 0.2 (0.1, 1.5) | 6.5 (6.5, 6.5) | 2.0 (1.3, 3.1) | 0.1 (0.1, 0.4) | 2.4 (0.5, 2.6) |
| Galactomanan dosing—sputum | 1/206 (0.5%) | 0/12 (0.0%) | 0/73 (0.0%) | 1/84 (1.2%) | 0/37 (0.0%) |
| LBA galactomannan dosing | 204/206 (99.0%) | 12/12 (100.0%) | 73/73 (100.0%) | 83/84 (98.8%) | 36/37 (97.3%) |
| Serum galactomannan dosing | 1/206 (0.5%) | 0/12 (0.0%) | 0/73 (0.0%) | 0/84 (0.0%) | 1/37 (2.7%) |
| Positive aspergillus culture in sputum | 32/328 (9.8%) | 1/25 (4.0%) | 3/105 (2.9%) | 18/135 (13.3%) | 10/63 (15.9%) |
| EORTC | Overall | Wave 1 | Wave 2 | Wave 3 | Wave 4 |
|---|---|---|---|---|---|
| Ruled out | 304/324 (93.8%) | 23/25 (92.0%) | 98/104 (94.2%) | 132/135 (97.8%) | 51/60 (85.0%) |
| Possible aspergillosis | 16/324 (4.9%) | 2/25 (8.0%) | 6/104 (5.8%) | 2/135 (1.5%) | 6/60 (10.0%) |
| Probable aspergillosis | 4/324 (1.2%) | 0/25 (0.0%) | 0/104 (0.0%) | 1/135 (0.7%) | 3/60 (5.0%) |
| ASPICU | |||||
| Ruled out | 293/328 (89.3%) | 24/25 (96.0%) | 103/105 (98.1%) | 114/135 (84.4%) | 52/63 (82.5%) |
| Colonization | 7/328 (2.1%) | 0/25 (0.0%) | 1/105 (1.0%) | 5/135 (3.7%) | 1/63 (1.6%) |
| Putative | 25/328 (7.6%) | 1/25 (4.0%) | 1/105 (1.0%) | 16/135 (11.9%) | 7/63 (11.1%) |
| Probable | 3/328 (0.9%) | 0/25 (0.0%) | 0/105 (0.0%) | 0/135 (0.0%) | 3/63 (4.8%) |
| ISHAM | |||||
| Ruled out | 275/324 (84.9%) | 24/25 (96.0%) | 96/105 (91.4%) | 110/135 (81.5%) | 45/59 (76.3%) |
| Possible | 9/324 (2.8%) | 0/25 (0.0%) | 2/105 (1.9%) | 4/135 (3.0%) | 3/59 (5.1%) |
| Probable | 40/324 (12.3%) | 1/25 (4.0%) | 7/105 (6.7%) | 21/135 (15.6%) | 11/59 (18.6%) |
| Recoded EORTC | Overall | Wave 1 | Wave 2 | Wave 3 | Wave 4 |
|---|---|---|---|---|---|
| 0 | 305/325 (93.8%) | 23/25 (92.0%) | 99/105 (94.3%) | 132/135 (97.8%) | 51/60 (85.0%) |
| 2 | 3/325 (0.9%) | 0/25 (0.0%) | 0/105 (0.0%) | 0/135 (0.0%) | 3/60 (5.0%) |
| 3 | 17/325 (5.2%) | 2/25 (8.0%) | 6/105 (5.7%) | 3/135 (2.2%) | 6/60 (10.0%) |
| Recoded AspICU criteria | |||||
| 0 | 293/328 (89.3%) | 24/25 (96.0%) | 103/105 (98.1%) | 114/135 (84.4%) | 52/63 (82.5%) |
| 1 | 7/328 (2.1%) | 0/25 (0.0%) | 1/105 (1.0%) | 5/135 (3.7%) | 1/63 (1.6%) |
| 3 | 28/328 (8.5%) | 1/25 (4.0%) | 1/105 (1.0%) | 16/135 (11.9%) | 10/63 (15.9%) |
| Recoded ISHAM criteria | |||||
| 0 | 275/324 (84.9%) | 24/25 (96.0%) | 96/105 (91.4%) | 110/135 (81.5%) | 45/59 (76.3%) |
| 2 | 9/324 (2.8%) | 0/25 (0.0%) | 2/105 (1.9%) | 4/135 (3.0%) | 3/59 (5.1%) |
| 3 | 40/324 (12.3%) | 1/25 (4.0%) | 7/105 (6.7%) | 21/135 (15.6%) | 11/59 (18.6%) |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Taleb, C.; Lelubre, C.; Biston, P.; Piagnerelli, M. Decoding CAPA: A Comparative Study of AspICU, ISHAM, and EORTC Criteria in Critical COVID-19 Patients Requiring Mechanical Ventilation. Microorganisms 2026, 14, 978. https://doi.org/10.3390/microorganisms14050978
Taleb C, Lelubre C, Biston P, Piagnerelli M. Decoding CAPA: A Comparative Study of AspICU, ISHAM, and EORTC Criteria in Critical COVID-19 Patients Requiring Mechanical Ventilation. Microorganisms. 2026; 14(5):978. https://doi.org/10.3390/microorganisms14050978
Chicago/Turabian StyleTaleb, Chahnez, Christophe Lelubre, Patrick Biston, and Michael Piagnerelli. 2026. "Decoding CAPA: A Comparative Study of AspICU, ISHAM, and EORTC Criteria in Critical COVID-19 Patients Requiring Mechanical Ventilation" Microorganisms 14, no. 5: 978. https://doi.org/10.3390/microorganisms14050978
APA StyleTaleb, C., Lelubre, C., Biston, P., & Piagnerelli, M. (2026). Decoding CAPA: A Comparative Study of AspICU, ISHAM, and EORTC Criteria in Critical COVID-19 Patients Requiring Mechanical Ventilation. Microorganisms, 14(5), 978. https://doi.org/10.3390/microorganisms14050978